Landing gear failure

A runway excursion involving a Fairchild Industries Metro 23 aircraft shows why it’s important that maintenance and inspection programs adequately provide for the detection of corrosion and cracking.

landing-gear-failure.jpg

On 20 February 2014, the aircraft was being operated on a charter flight from Avalon to Portland, Victoria with 10 passengers and two crew on board.

Shortly after touch-down, the torque link on the left, main landing gear (MLG) failed. This resulted in the aircraft veering left and coming to rest beside the runway. Fortunately no one was injured.

The runway excursion resulted from failure of the lower torque link attachment lug on the left main landing gear’s yoke. This allowed the wheels to rotate through 90 degrees, producing a large braking effect on the left side.

The flight crew were unable to counteract this and the aircraft veered to the left and off the runway.

The failure of the lug on the yoke resulted from pre-existing cracks that had progressively grown until the part had insufficient strength to support normal landing loads.

The cracks initiated principally from areas of pitting corrosion in the lug’s bore and were propagated by cyclic stresses imposed during operation.

The ATSB found the maintenance and inspection program for the aircraft’s landing gear did not adequately provide for the detection of corrosion and cracking in the yoke lug bore.

This occurrence highlights the importance of developing and conducting appropriately detailed maintenance inspections on susceptible parts and assemblies.

The Civil Aviation Safety Authority (CASA) has released Airworthiness Bulletin AWB 32-023 to alert all Fairchild Swearingen Metro and Merlin operators of the need for detailed inspection of the internal bore of the landing gear torque link lugs for any signs of corrosion or wear outside of the manufacturer’s specified limits and to take appropriate action per the aircraft’s structural repair manual, where necessary.

In addition, the aircraft’s Type Certificate Holder has drafted service bulletins 226-32-083, 227-32-065, CC7-32-030 titled “inspection of Main Landing Yoke for Corrosion and/or Damage” that will significantly increase the effectiveness of maintenance inspections for the affected parts.

This occurrence highlights the importance of developing and conducting appropriately detailed maintenance inspections on susceptible parts and assemblies.

Read the final report: Runway excursion involving a Fairchild Metro 23, VH-UUB, at Portland, Victoria, on 20 February 2014


Fire on board!

This shipboard fire quickly got out of control causing extensive damage and several injuries due to smoke inhalation. An open cabin door and a stairwell fire door left hooked open were contributing factors.

oceandrover-fire_news.jpg

On the morning of 9 October 2014, a fire started in Ocean Drover’s crew accommodation while the livestock carrier was berthed in Fremantle, Western Australia. The fire quickly spread across both accommodation decks. The ship’s crew and shore emergency response teams responded, and fire-fighting efforts continued for the rest of the day.

By the time the fire was extinguished late that evening, the ship’s accommodation areas and its navigation bridge had been extensively damaged. Four of the ship’s crew sustained injuries that required medical treatment.

The ATSB found that the fire started in a centrally located forward cabin on Ocean Drover’s upper deck. The intensity of the fire and the severity of the damage made it impossible to identify an exact point of origin or source of the fire.

The ATSB investigation found that the cabin door was left open after the fire was discovered allowing smoke and flame to spread beyond the cabin. Further, the bridge deck stairwell fire door was hooked open, which allowed the fire to rapidly spread and engulf both the upper and bridge decks.

The investigation also identified that the ship’s crew did not complete a muster and accurate head count when responding to the fire.

While cigarette smoking was not identified as a contributing factor, it was found that the smoking policy and associated risk controls on board were not effectively managed.

Ocean Drover underwent extensive post-fire repairs before it could return to service. During the repair period, the ship’s managers took pro-active safety action to avoid a similar incident in the future. All cabins in the ship’s accommodation were fitted with smoke detectors. The bridge deck stairwell fire door was replaced with one that is not fitted with a hold back arrangement (to comply with mandatory regulations). Notices posted on both sides of the door require it to be kept closed.

The ship’s managers have revised the shipboard smoking policy and restricted smoking to designated rooms, which exclude crew cabins. Designated smoking rooms are provided with safety ashtrays and sand bins, and warning signs have been posted in accommodation areas. The managers promulgated the lessons learned from the fire and safety action taken across the fleet through procedural changes and safety meetings.

Safety message

Containing a shipboard fire in the compartment where it originates is critical to firefighting.

Effective containment relies on maintaining the integrity of fire divisions, including bulkheads, decks and doors. In this regard, particular attention must be paid to ensuring fire doors, designed to limit or prevent the spread of fire, are never latched/lashed open, or otherwise compromised.

Read the final report: Fire on board the livestock carrier Ocean Drover, Fremantle, Western Australia, on 9 October 2014

Track worker fatally struck by train

A track worker who was fatally struck by a passenger train in Guildford, Western Australia had no form of protection such as a lookout, at the work site, according to the ATSB’s final investigation report.

ro-2015002_accident-intersection.jpg

On 10 February 2015, a Public Transport Authority (PTA) maintenance crew commenced work at Meadow Street in Guildford. The crew was maintaining the pedestrian gates adjacent to the level crossing.

At about 10.35 am, one of the track workers was struck by a Perth-bound suburban passenger train. Tragically, the track worker died in the accident.

The ATSB investigation found that the PTA maintenance workers had not implemented any form of track worker protection at the work site. This was partially due to the PTA not having documented instructions specifying the level of protection required, preferring that track workers make their own assessment based on their knowledge of the Network Rules. The ATSB found that, under these arrangements, track workers could make an incorrect assessment, placing themselves at a greater risk of being struck by a train.

A review of the safeworking training provided to the track workers found that the training material did provide a suitable level of safe-working knowledge.

Following the occurrence, the toxicology report on the deceased track worker identified the presence of amphetamine and methamphetamine; methamphetamine being a prescribed drug under the Rail Safety Regulations 2011. The use of stimulants such as methamphetamine is associated with a range of neurocognitive effects in humans that may affect performance.

The ATSB found that in this instance, the presence of a prescribed drug within the worker’s system appeared to be a relatively isolated case. An examination of the company’s drug and alcohol policy/procedures found them to be generally effective in managing drugs and alcohol in the workplace.

The PTA issued a safety alert following the incident to highlight the importance of implementing the correct level of track worker protection. The subsequent introduction of new safeworking rules, track access accreditation levels and training further supported this.

Further, the PTA has created the role of Workplace trainer and assessor with the task of ensuring track workers comply with the network rules by way of competency-based assessments. Implementation of a new track access accreditation system, with improved training and job mentoring, has also commenced.  

Safety message

This incident strongly emphasises the need for rail transport operators to provide clear and concise work instructions to employees working within the railway corridor. It also highlights the potential for recreational and other drug use to impair performance and affect workplace safety.

Read the final report: Collision between track worker and passenger train, Guildford, Western Australia, on 10 February 2015

Learn more about Safe work on rail

Oil on windscreen

Oil on the windscreen due to an unsecured engine oil filler cap prompted the pilot of a Cessna T210N to attempt a go-around, with tragic results.

cessna_vh-zfw_news.jpg

On 4 July 2014, the owner/pilot of a Cessna aircraft and two passengers were conducting a private flight from Inverell Airport to Bankstown Airport, New South Wales.

Shortly after take-off, oil appeared on the windscreen and the pilot rejected the take-off with the intent of landing back on the runway.

With the oil obscuring the pilot’s forward vision, the pilot looked to the left of the aircraft to assess their position along the runway. The pilot realised they were a lot further along the runway than expected and had insufficient runway distance to land safely. The pilot attempted a go-around but later reported the engine did not respond. During the subsequent forced landing, the aircraft impacted a shrub beyond the end of the runway overrun and flipped, before coming to rest inverted.

The pilot and a passenger were hospitalised with serious injuries and the second passenger received minor injuries. Tragically, the seriously-injured passenger later succumbed to their injuries. The aircraft was destroyed by the impact forces and a post-impact fuel-fed fire.

Examination of the aircraft found the engine oil filler cap detached from the oil filler tube but hanging by its chain. Further examination of the tube and cap determined that it was most likely the cap was not secure before the flight commenced.

The Cessna T210N pilot’s operating handbook advised pilots to check the engine oil level during a pre‑flight inspection but not the security of the separate oil filler cap. The ATSB could not establish the extent to which a specific checklist item about oil filler cap security would have assisted in identifying the unsecured cap in this case, although it would probably have increased the likelihood of detection.

Witness observations and the pilot’s assessment of the aircraft’s position along the runway during the rejected take-off indicated that the take-off was longer than normal. The reason for this could not be determined.

Examination of the engine and turbocharger found no mechanical defect or failure that would have precluded normal operation. While it was possible that a temporary issue occurred, resulting in the reported lack of engine response during the go-around, this could not be established.

The ATSB also determined that the engine manufacturer’s oil change interval had been exceeded by 3 months but it was very unlikely that this had any effect on the operation of the engine.

Safety message

This accident highlights that, prior to take-off, pilots should have in mind a go/no-go decision point along the runway by which time the aircraft should become airborne. If at that point the aircraft is not airborne, the pilot should reject the take-off. Having such a point assists pilot decision making during a critical phase of flight. This is particularly important when operating in conditions that may affect aircraft performance, such as tailwind conditions.

In addition, the ATSB highlights the importance of being aware of the daily inspection requirements when operating aircraft under a CASA maintenance schedule. In particular, how this may differ from the aircraft manufacturer’s pre-flight inspection procedure.

Read the final report: Collision with terrain involving Cessna T210N, VH-ZFW, near Inverell Airport, New South Wales, on 4 July 2014

Unexpected developments

A recent ATSB investigation shows how unexpected developments or confusion about procedures can contribute to decisions and actions that increase the safety risk to the aircraft.

qantasjet_news.jpg

In the incident, the crew of a Cobham Airline Services Boeing 717 aircraft, was conducting an instrument approach to land on runway 03 at Perth Airport.

The aircraft was conducting an approach in instrument meteorological conditions after a flight from Paraburdoo, Western Australia. When they reached the decision altitude, the crew initiated a missed approach procedure as they had not obtained visual reference with the runway.

Almost immediately, however, they obtained visual reference with the runway, discontinued the missed approach procedure and landed, despite the aircraft being in an unstable condition.

The ATSB found that the onset of fog at Perth Airport at the estimated time of arrival was not forecast until after the aircraft had passed the point in the flight when it had insufficient fuel remaining to divert to a suitable alternate aerodrome. Before that point, there had been no requirement for the aircraft to carry fuel to continue to a suitable alternate.

Under the circumstances, the flight crew considered that the better option was to discontinue the missed approach procedure and land, in spite of the aircraft being in an unstable condition due to the initiation of the missed approach.

This incident highlights the risk of an unstable approach from not following a missed approach through to its conclusion.

Unstable approaches are a frequent factor in approach and landing accidents, including controlled flight into terrain. The Flight Safety Foundation has developed an Approach and Landing Accident Reduction Tool Kit(Opens in a new tab/window) to reduce the risk of approach and landing accidents.

Handling approach to land’ is also a top safety concern in the ATSB’s SafetyWatch initiative. The ATSB has identified an increasing trend where pilots mishandle or mismanage their aircraft and flight profile when unexpected events arise during the approach to land.

The occurrence also highlights that during a flight, the forecast weather at the destination may change and it is advisable to obtain the most up-to-date weather forecasts. However, pilots should be alert to the fact that the actual weather can differ significantly from forecasts.

Read the final report: Weather-related operational event involving Boeing 717, VH NXO, Perth Airport, Western Australia, on 1 June 2012

Prepared for the worst

  • It pays to have a plan if things start to go wrong - in this case the pilot made all the right moves.
gippsland-aeronautics-ga-8_news.jpg

On 21 October 2015, a Gippsland Aeronautics GA-8 aircraft was conducting parachute operations at Busselton Airport, Western Australia.

The aircraft took off with a pilot and seven parachutists on board. As it climbed through about 2,000 ft, the pilot observed a decrease in the engine manifold pressure. The fuel flow also increased significantly. As the aircraft was tracking south towards forested terrain, the pilot elected to turn back towards the aerodrome, and continue the climb, in case the engine issue worsened. The pilot conducted the standard engine checks, but the engine continued to produce only partial power. In response the pilot broadcast a Mayday.

The pilot advised the parachutists they would establish the aircraft in the drop run overhead the aerodrome at about 4,000 ft. As the pilot subsequently reduced the power to allow the parachutists to exit the aircraft, the engine ran roughly. Six of the parachutists exited normally and landed safely at the drop zone, while the seventh, who was also a company pilot and seated in the front passenger seat, remained in the aircraft with the pilot in command.

The pilot then increased the aircraft’s power until the engine ran smoothly, although only producing partial power, while continuing the descent to the aerodrome. The pilot also advised Air Traffic Control that they did not require immediate assistance and downgraded to a PAN, as the engine continued to produce some power. The aircraft landed safely at Busselton.

After shutting down the engine, the pilot consulted with the maintainer, and found that the intake tube on the No. 4 cylinder was loose. 

A reminder that constant monitoring of the engine instruments can provide early indication of a problem.

This incident highlights the importance of having thoroughly rehearsed emergency procedures, particularly for parachute operations.The parachutists had, in accordance with standard procedures, removed the single point restraints during the climb, and were prepared to exit the aircraft quickly.

For pilots, this provides a reminder that constant monitoring of the engine instruments can provide early indication of a problem. Acting quickly on this information may reduce the impact of partial or total power loss on flight safety.

The ATSB publication Avoidable Accidents No. 3 – Managing partial power loss after take-off in single-engine aircraft, provides information also relevant to partial losses of power in flight as well as after take-off. Following a complete engine failure, a forced landing is inevitable. For a partial power loss, pilots are faced with deciding whether to continue the flight or land immediately.

Read the final report: Partial engine failure involving a Gippsland Aeronautics GA-8, VH-FGN, near Busselton Airport, Western Australia, on 21 October 2015

Wildlife strikes pose risk

Wildlife strikes are among the most common occurrences reported to the ATSB. They are a significant safety risk for pilots as well as an economic risk for aerodrome and airline operators.

Two recent incidents illustrate how quickly and unexpectedly damage can occur to aircraft.

On 1 September 2015, the pilot of a SA227 (Metroliner) aircraft was conducting a scheduled freight run from Brisbane to Emerald via Thangool Airport, Queensland.

Shortly after touchdown, and with all landing gear wheels in contact with the ground, the pilot saw the glimpse of an animal flash from left to right in front of the aircraft. At the time, the aircraft was travelling at about 80 kt.

The right propeller then struck the animal, later identified as a small kangaroo. The pilot reported that following the large bang associated with the propeller striking the animal, there was a lot of vibration throughout the aircraft, but no abnormal engine indications. The pilot continued the landing roll, and used ground idle rather than reverse thrust to slow the aircraft.

The pilot taxied the aircraft to the parking bay, shut down the engines, then carried out an external inspection. One of the propeller blades attached to the right engine was twisted. Luckily the pilot escaped injury.

Although the Thangool airport had wildlife protective fencing, at the time it wasn’t fully fenced. There had been no reported kangaroo strikes in the last 28 years, and a runway inspection had just been conducted 20 minutes prior to the landing.

ao-2015-102.jpg

On 2 September 2015, another strike was reported by a Raytheon B200 aircraft on a medical retrieval mission from Townsville to Barcaldine Airport, Queensland.

When touching down in the early hours of the morning, the pilot caught a last moment glimpse of a small kangaroo before the aircraft struck the animal.

The pilot reported that engine indications were normal, with no noticeable vibration as they completed the landing roll and then shut down the left engine while on the runway. They then taxied clear of the runway using the remaining engine.

The strike caused damage to the three propeller blades attached to the left engine and disabled the aircraft. No one on-board the aircraft was injured.

The ATSB regularly publishes a statistical report on the number and frequency of wildlife strikes. This report provides information for pilots, aerodrome and airline operators, regulators, and other aviation industry participants to assist with managing the risks associated with bird and animal strikes.

Both animal strikes and bird strikes remain a mandatory reporting item under the Transport Safety Investigation Act 2003.

Read the final report: Collisions with kangaroos involving a Fairchild SA227 (Metroliner), VH-HPE, Thangool Airport, Queensland, on 1 September 2015, and a King Air B200, VH-FDB, Barcaldine Airport, Queensland, on 2 September 2015

Good fuel management saves the day

This incident shows how a pilot’s good fuel management ensured the safe landing of a Piper Chieftain aircraft after an unexpected incident.

piperchieftain.jpg

On 12 October 2015, the pilot and three passengers were conducting a survey flight over the southern highlands area of New South Wales.

After departure, the pilot reported that clouds (both towering cumulus and cumulus) were beginning to form in the area, producing some light turbulence. The pilot remained concerned about one of the passengers, seated at the rear of the aircraft, who appeared to find the conditions difficult to tolerate.

The pilot’s workload remained high. Apart from flying to each of the pre-arranged waypoints, additional landmarks were being relayed to the pilot from the client’s operator on the ground.

The pilot kept a very detailed fuel log, and continually cross-checked the fuel in each of the four fuel tanks. The weather had deteriorated even further as the pilot prepared to fly to the last waypoint before a return to Bankstown. The pilot delayed a scheduled fuel tank change to maximise the fuel remaining in the main (inboard) tanks.

As the pilot was maneuvering around large banks of cloud and thunderstorms, the left auxiliary (outboard) tank ran dry and the engine surged. The aircraft yawed. The pilot reacted immediately and changed the fuel selectors onto the main tanks. The engine responded and power was restored. The aircraft returned to Bankstown without incident.

In this incident, the pilot followed all the key suggestions in the ATSB’s Avoidable Accident Series No 5 – Starved and exhausted: Fuel management aviation accidents. These being

  • Knew exactly how much fuel was on board
  • Knew how much / what rate fuel was being consumed
  • Knew the aircraft fuel system and keep a detailed fuel log of the four tanks during flight.

Despite a high workload, deteriorating weather, and untimely distractions the pilot was well prepared to handle an unplanned outcome of temporary fuel starvation of the left engine.

Read the final report: Fuel management issue involving a PA31-350, VH-HJH, 19 km north of Goulburn Airport, New South Wales, on 12 October 2015

Routine task ends in fatality

Hyundai-Dangjin_newsitem.jpg

A tragic man overboard fatality shows why it’s vital that mariners always plan properly for all tasks, no matter how seemingly straight forward or routine. 

The tragedy unfolded on 10 July 2015 when Hyundai Dangjin was in the final stages of loading its cargo of iron ore at Port Walcott, Western Australia. The ship was starboard side alongside the wharf and the chief mate and draught surveyor were on the wharf to check the ship’s draught. (The draught is the distance between the surface of the water and the lowest point of the ship).

They could see the forward and aft draught marks but not the midships marks.

At 0450, the chief mate asked the second mate, via UHF radio, to read the midships draught on the ship’s port (outboard) side. The ship’s crew had already rigged a rope ladder adjacent to the draught marks there.

In preparation to climb down the rope ladder, the second mate donned a life vest (non-inflatable flotation aid). The able seaman (AB) on duty offered to go down the ladder instead of the second mate, who was a large and heavy man. The second mate declined the AB’s offer (mates are trained to read draught marks).

Just after 0455, the chief mate and draught surveyor returned from the wharf to the ship’s office. The chief mate then called the second mate and asked for the midships draught. The second mate did not reply.

At that time, the second mate was near the bottom of the ladder, about 7 m below the ship’s deck. He called out to the AB for help and said he was having difficulty. When the AB checked, he saw the second mate struggling to hold on to the ladder. As the AB looked around for a rope to throw down, the second mate fell into the water. The AB threw a nearby lifebuoy to the second mate and it landed a few metres away.

The second mate tried to swim to the lifebuoy, but was not able to reach it. The sea was rough (1.4 m sea on a 0.4 m swell) and the water temperature was about 22 °C.

The ATSB found the rope ladder had been rigged upside down. With their wrong side up, the ladder steps (folded aluminium) did not provide a flat surface to stand on comfortably. Further, the steps were not good handholds.

The sole precaution taken by the second mate while reading the draught marks was his life vest. No fall prevention measures were put in place or used. The life vest’s specifications could not be determined but similar types provide around 7 to 10 kg of buoyancy.

Safety message

In many cases, little attention is paid to planning apparently straightforward tasks, such as using a rope ladder. This can lead to important factors and relevant considerations not being taken into account, including the experience and physical ability of persons undertaking the task.

The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported by industry. Marine work practices is one of those safety concerns.

Read the final report: Man overboard fatality from Hyundai Dangjin, Port Walcott, Western Australia, on 10 July 2015

Carburettor icing risk warning

Carburettor icing likely resulted in the engine failure that led to the crash of an amateur‑built Van’s Aircraft RV-6 two-seat aeroplane. Tragically the pilot and passenger died in the accident.

Vans_ao-2014-149_news.jpg

On 14 September 2014 a Van's Aircraft RV-6 aircraft, operated in the ‘Experimental’ category, was approaching Mudgee Airport after departing Dubbo Airport, New South Wales about 25 minutes earlier.

The pilot approached from the north-west and conducted a non-standard circuit entry including an orbit to the south of the airport. Prior to turning onto the downwind leg of the circuit, the aeroplane descended to about 600 ft above ground level. Witnesses stated the pilot conducted a tight left turn onto final approach at a slow speed and low height. Witnesses also recalled hearing the aircraft’s engine ‘splutter’ and then go silent during the turn, followed by a ‘rev’, and then again silence.

The aircraft continued its high angle of bank left turn and then collided with terrain about 300 m south-west and short of the runway threshold. The pilot and passenger were fatally injured and the aeroplane was substantially damaged.

The ATSB found that during the turn onto final approach to land, the aeroplane’s engine ceased operating. The aeroplane’s airspeed before the engine failure was within about 0.5 kt of the estimated stall speed during the high-bank turn. After the engine failure, it is likely the aeroplane entered an aerodynamic stall. The associated loss of control was not recovered and the aircraft continued in the turn until it collided with terrain.

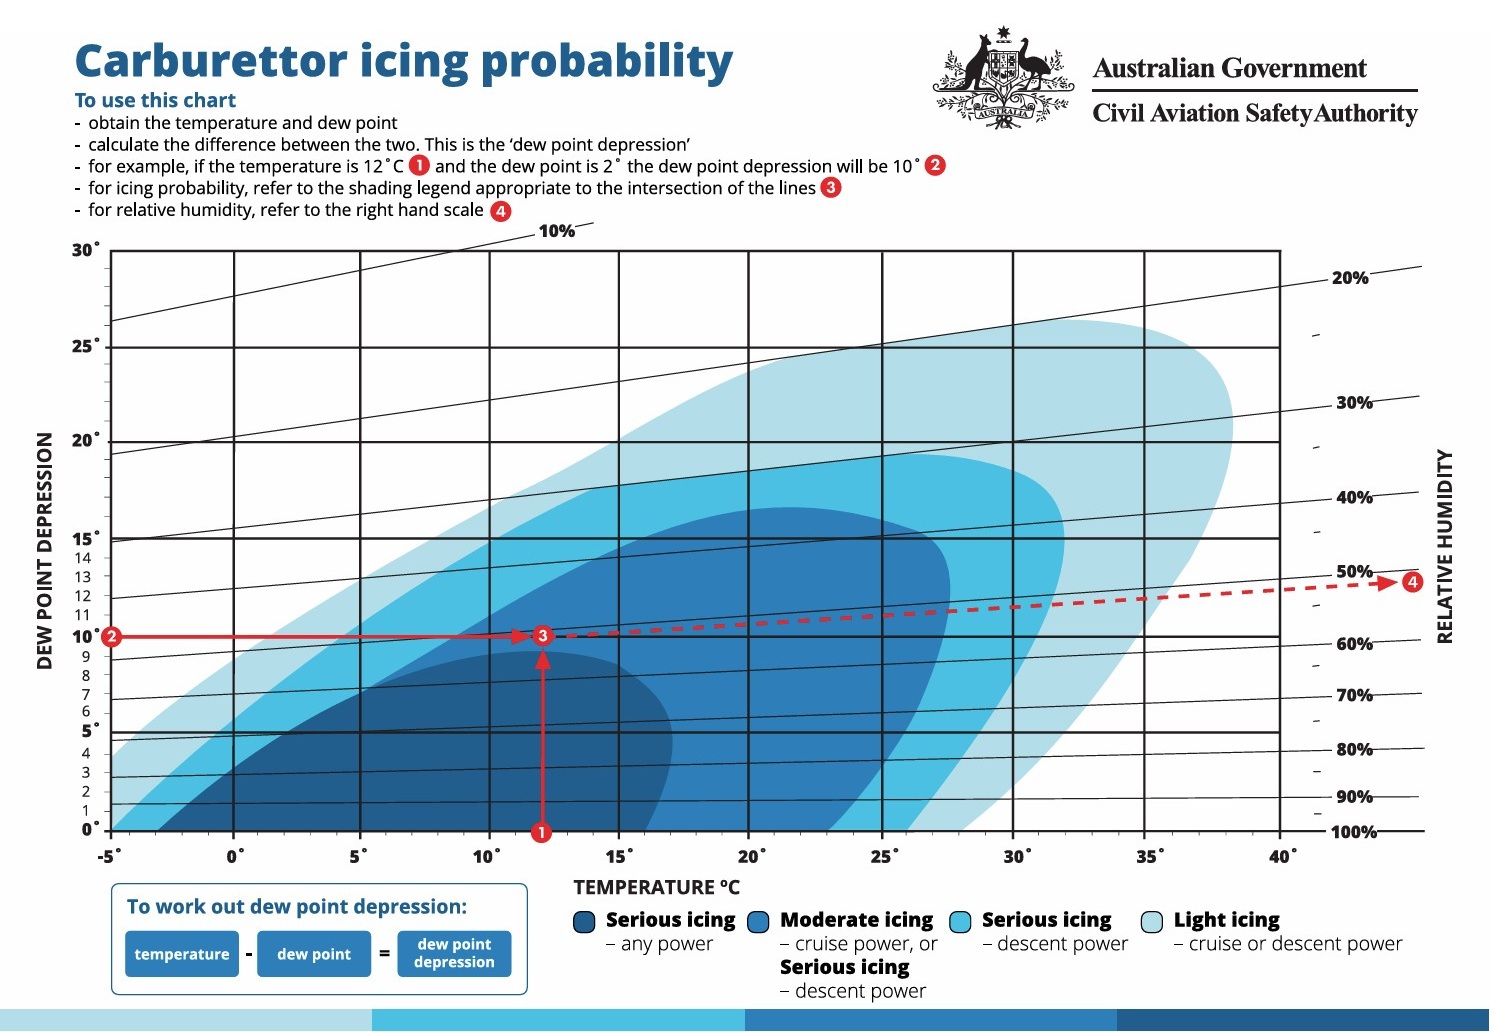
The ATSB also found that the engine failure was probably due to carburettor icing. No defects were identified that would have precluded normal engine operation prior to the accident, and uncontaminated fuel was being supplied to the engine at that time. However, the environmental conditions at the time of the accident were conducive to serious carburettor icing at descent power, and the pilot-operated carburettor heat control was found in the OFF position.

The ATSB also found that the aeroplane’s weight was higher than the design limits. However, the effect of this weight on aircraft performance was not considered to have contributed to the accident.

The aeroplane was not required to be, and was not fitted with an angle-of-attack indicator or stall warning device.

All pilots of aircraft fitted with a carburettor are advised to check the forecast weather conditions and consider the risk of carburettor icing as a result of those conditions prior to each flight.

Although amateur-built aeroplanes operated in the Experimental category are not required to be fitted with a stall warning device, owner-pilots should consider the benefits of such devices as a last line of defence against the inadvertent approach to, or entry into an aerodynamic stall.

Read the final report: Collision with terrain involving Van's Aircraft RV-6, VH-TXF, near Mudgee Airport, New South Wales, on 14 September 2014

Carburettor icing probability chart.jpg