Prepared for the worst

  • It pays to have a plan if things start to go wrong - in this case the pilot made all the right moves.

gippsland-aeronautics-ga-8_news.jpg

On 21 October 2015, a Gippsland Aeronautics GA-8 aircraft was conducting parachute operations at Busselton Airport, Western Australia.

The aircraft took off with a pilot and seven parachutists on board. As it climbed through about 2,000 ft, the pilot observed a decrease in the engine manifold pressure. The fuel flow also increased significantly. As the aircraft was tracking south towards forested terrain, the pilot elected to turn back towards the aerodrome, and continue the climb, in case the engine issue worsened. The pilot conducted the standard engine checks, but the engine continued to produce only partial power. In response the pilot broadcast a Mayday.

The pilot advised the parachutists they would establish the aircraft in the drop run overhead the aerodrome at about 4,000 ft. As the pilot subsequently reduced the power to allow the parachutists to exit the aircraft, the engine ran roughly. Six of the parachutists exited normally and landed safely at the drop zone, while the seventh, who was also a company pilot and seated in the front passenger seat, remained in the aircraft with the pilot in command.

The pilot then increased the aircraft’s power until the engine ran smoothly, although only producing partial power, while continuing the descent to the aerodrome. The pilot also advised Air Traffic Control that they did not require immediate assistance and downgraded to a PAN, as the engine continued to produce some power. The aircraft landed safely at Busselton.

After shutting down the engine, the pilot consulted with the maintainer, and found that the intake tube on the No. 4 cylinder was loose. 

A reminder that constant monitoring of the engine instruments can provide early indication of a problem.

This incident highlights the importance of having thoroughly rehearsed emergency procedures, particularly for parachute operations.The parachutists had, in accordance with standard procedures, removed the single point restraints during the climb, and were prepared to exit the aircraft quickly.

For pilots, this provides a reminder that constant monitoring of the engine instruments can provide early indication of a problem. Acting quickly on this information may reduce the impact of partial or total power loss on flight safety.

The ATSB publication Avoidable Accidents No. 3 – Managing partial power loss after take-off in single-engine aircraft, provides information also relevant to partial losses of power in flight as well as after take-off. Following a complete engine failure, a forced landing is inevitable. For a partial power loss, pilots are faced with deciding whether to continue the flight or land immediately.

Read the final report: Partial engine failure involving a Gippsland Aeronautics GA-8, VH-FGN, near Busselton Airport, Western Australia, on 21 October 2015


Wildlife strikes pose risk

Wildlife strikes are among the most common occurrences reported to the ATSB. They are a significant safety risk for pilots as well as an economic risk for aerodrome and airline operators.

Two recent incidents illustrate how quickly and unexpectedly damage can occur to aircraft.

On 1 September 2015, the pilot of a SA227 (Metroliner) aircraft was conducting a scheduled freight run from Brisbane to Emerald via Thangool Airport, Queensland.

Shortly after touchdown, and with all landing gear wheels in contact with the ground, the pilot saw the glimpse of an animal flash from left to right in front of the aircraft. At the time, the aircraft was travelling at about 80 kt.

The right propeller then struck the animal, later identified as a small kangaroo. The pilot reported that following the large bang associated with the propeller striking the animal, there was a lot of vibration throughout the aircraft, but no abnormal engine indications. The pilot continued the landing roll, and used ground idle rather than reverse thrust to slow the aircraft.

The pilot taxied the aircraft to the parking bay, shut down the engines, then carried out an external inspection. One of the propeller blades attached to the right engine was twisted. Luckily the pilot escaped injury.

Although the Thangool airport had wildlife protective fencing, at the time it wasn’t fully fenced. There had been no reported kangaroo strikes in the last 28 years, and a runway inspection had just been conducted 20 minutes prior to the landing.

ao-2015-102.jpg

On 2 September 2015, another strike was reported by a Raytheon B200 aircraft on a medical retrieval mission from Townsville to Barcaldine Airport, Queensland.

When touching down in the early hours of the morning, the pilot caught a last moment glimpse of a small kangaroo before the aircraft struck the animal.

The pilot reported that engine indications were normal, with no noticeable vibration as they completed the landing roll and then shut down the left engine while on the runway. They then taxied clear of the runway using the remaining engine.

The strike caused damage to the three propeller blades attached to the left engine and disabled the aircraft. No one on-board the aircraft was injured.

The ATSB regularly publishes a statistical report on the number and frequency of wildlife strikes. This report provides information for pilots, aerodrome and airline operators, regulators, and other aviation industry participants to assist with managing the risks associated with bird and animal strikes.

Both animal strikes and bird strikes remain a mandatory reporting item under the Transport Safety Investigation Act 2003.

Read the final report: Collisions with kangaroos involving a Fairchild SA227 (Metroliner), VH-HPE, Thangool Airport, Queensland, on 1 September 2015, and a King Air B200, VH-FDB, Barcaldine Airport, Queensland, on 2 September 2015

Good fuel management saves the day

This incident shows how a pilot’s good fuel management ensured the safe landing of a Piper Chieftain aircraft after an unexpected incident.

piperchieftain.jpg

On 12 October 2015, the pilot and three passengers were conducting a survey flight over the southern highlands area of New South Wales.

After departure, the pilot reported that clouds (both towering cumulus and cumulus) were beginning to form in the area, producing some light turbulence. The pilot remained concerned about one of the passengers, seated at the rear of the aircraft, who appeared to find the conditions difficult to tolerate.

The pilot’s workload remained high. Apart from flying to each of the pre-arranged waypoints, additional landmarks were being relayed to the pilot from the client’s operator on the ground.

The pilot kept a very detailed fuel log, and continually cross-checked the fuel in each of the four fuel tanks. The weather had deteriorated even further as the pilot prepared to fly to the last waypoint before a return to Bankstown. The pilot delayed a scheduled fuel tank change to maximise the fuel remaining in the main (inboard) tanks.

As the pilot was maneuvering around large banks of cloud and thunderstorms, the left auxiliary (outboard) tank ran dry and the engine surged. The aircraft yawed. The pilot reacted immediately and changed the fuel selectors onto the main tanks. The engine responded and power was restored. The aircraft returned to Bankstown without incident.

In this incident, the pilot followed all the key suggestions in the ATSB’s Avoidable Accident Series No 5 – Starved and exhausted: Fuel management aviation accidents. These being

  • Knew exactly how much fuel was on board
  • Knew how much / what rate fuel was being consumed
  • Knew the aircraft fuel system and keep a detailed fuel log of the four tanks during flight.

Despite a high workload, deteriorating weather, and untimely distractions the pilot was well prepared to handle an unplanned outcome of temporary fuel starvation of the left engine.

Read the final report: Fuel management issue involving a PA31-350, VH-HJH, 19 km north of Goulburn Airport, New South Wales, on 12 October 2015

Routine task ends in fatality

Hyundai-Dangjin_newsitem.jpg

A tragic man overboard fatality shows why it’s vital that mariners always plan properly for all tasks, no matter how seemingly straight forward or routine. 

The tragedy unfolded on 10 July 2015 when Hyundai Dangjin was in the final stages of loading its cargo of iron ore at Port Walcott, Western Australia. The ship was starboard side alongside the wharf and the chief mate and draught surveyor were on the wharf to check the ship’s draught. (The draught is the distance between the surface of the water and the lowest point of the ship).

They could see the forward and aft draught marks but not the midships marks.

At 0450, the chief mate asked the second mate, via UHF radio, to read the midships draught on the ship’s port (outboard) side. The ship’s crew had already rigged a rope ladder adjacent to the draught marks there.

In preparation to climb down the rope ladder, the second mate donned a life vest (non-inflatable flotation aid). The able seaman (AB) on duty offered to go down the ladder instead of the second mate, who was a large and heavy man. The second mate declined the AB’s offer (mates are trained to read draught marks).

Just after 0455, the chief mate and draught surveyor returned from the wharf to the ship’s office. The chief mate then called the second mate and asked for the midships draught. The second mate did not reply.

At that time, the second mate was near the bottom of the ladder, about 7 m below the ship’s deck. He called out to the AB for help and said he was having difficulty. When the AB checked, he saw the second mate struggling to hold on to the ladder. As the AB looked around for a rope to throw down, the second mate fell into the water. The AB threw a nearby lifebuoy to the second mate and it landed a few metres away.

The second mate tried to swim to the lifebuoy, but was not able to reach it. The sea was rough (1.4 m sea on a 0.4 m swell) and the water temperature was about 22 °C.

The ATSB found the rope ladder had been rigged upside down. With their wrong side up, the ladder steps (folded aluminium) did not provide a flat surface to stand on comfortably. Further, the steps were not good handholds.

The sole precaution taken by the second mate while reading the draught marks was his life vest. No fall prevention measures were put in place or used. The life vest’s specifications could not be determined but similar types provide around 7 to 10 kg of buoyancy.

Safety message

In many cases, little attention is paid to planning apparently straightforward tasks, such as using a rope ladder. This can lead to important factors and relevant considerations not being taken into account, including the experience and physical ability of persons undertaking the task.

The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported by industry. Marine work practices is one of those safety concerns.

Read the final report: Man overboard fatality from Hyundai Dangjin, Port Walcott, Western Australia, on 10 July 2015

Carburettor icing risk warning

Carburettor icing likely resulted in the engine failure that led to the crash of an amateur‑built Van’s Aircraft RV-6 two-seat aeroplane. Tragically the pilot and passenger died in the accident.

Vans_ao-2014-149_news.jpg

On 14 September 2014 a Van's Aircraft RV-6 aircraft, operated in the ‘Experimental’ category, was approaching Mudgee Airport after departing Dubbo Airport, New South Wales about 25 minutes earlier.

The pilot approached from the north-west and conducted a non-standard circuit entry including an orbit to the south of the airport. Prior to turning onto the downwind leg of the circuit, the aeroplane descended to about 600 ft above ground level. Witnesses stated the pilot conducted a tight left turn onto final approach at a slow speed and low height. Witnesses also recalled hearing the aircraft’s engine ‘splutter’ and then go silent during the turn, followed by a ‘rev’, and then again silence.

The aircraft continued its high angle of bank left turn and then collided with terrain about 300 m south-west and short of the runway threshold. The pilot and passenger were fatally injured and the aeroplane was substantially damaged.

The ATSB found that during the turn onto final approach to land, the aeroplane’s engine ceased operating. The aeroplane’s airspeed before the engine failure was within about 0.5 kt of the estimated stall speed during the high-bank turn. After the engine failure, it is likely the aeroplane entered an aerodynamic stall. The associated loss of control was not recovered and the aircraft continued in the turn until it collided with terrain.

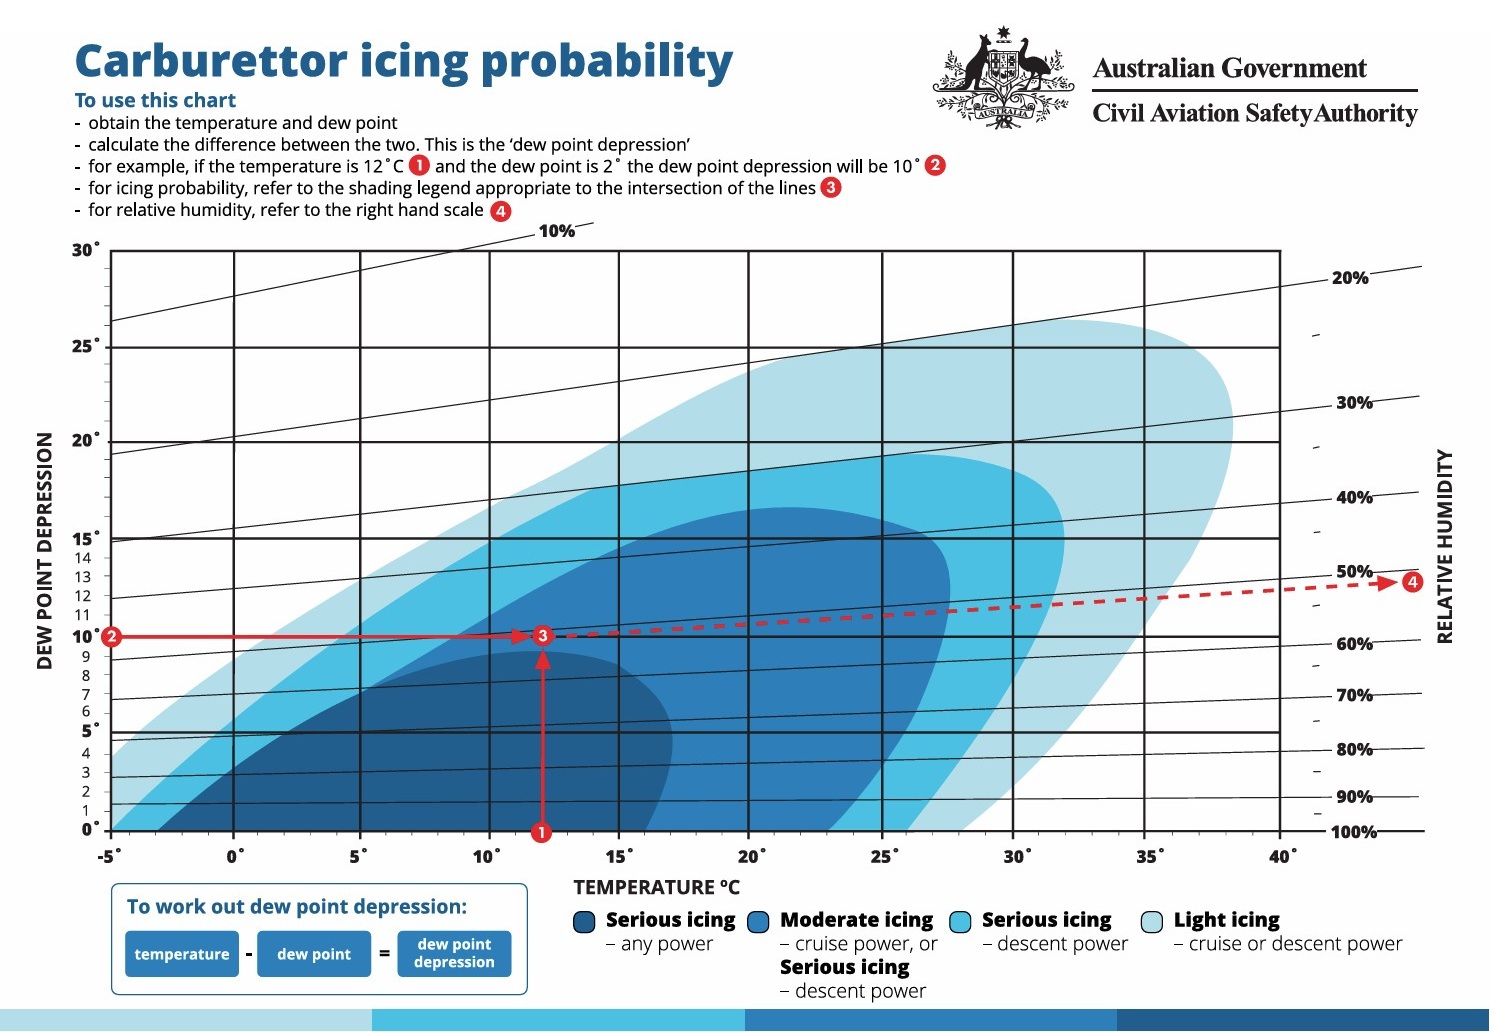
The ATSB also found that the engine failure was probably due to carburettor icing. No defects were identified that would have precluded normal engine operation prior to the accident, and uncontaminated fuel was being supplied to the engine at that time. However, the environmental conditions at the time of the accident were conducive to serious carburettor icing at descent power, and the pilot-operated carburettor heat control was found in the OFF position.

The ATSB also found that the aeroplane’s weight was higher than the design limits. However, the effect of this weight on aircraft performance was not considered to have contributed to the accident.

The aeroplane was not required to be, and was not fitted with an angle-of-attack indicator or stall warning device.

All pilots of aircraft fitted with a carburettor are advised to check the forecast weather conditions and consider the risk of carburettor icing as a result of those conditions prior to each flight.

Although amateur-built aeroplanes operated in the Experimental category are not required to be fitted with a stall warning device, owner-pilots should consider the benefits of such devices as a last line of defence against the inadvertent approach to, or entry into an aerodynamic stall.

Read the final report: Collision with terrain involving Van's Aircraft RV-6, VH-TXF, near Mudgee Airport, New South Wales, on 14 September 2014

Carburettor icing probability chart.jpg

Trains collide

RO-2015-007_news-item.jpg

A train collision, resulting in the derailment of three wagons, highlights the importance of good communications in reducing the risk of collision.    

On 31 March 2015, freight train 2MP9 collided with the rear end of stationary freight train (2MP1) at Mile End, South Australia. The collision resulted in moderate track damage and the derailment of three wagons at the rear of train 2MP1. Fortunately, there were no injuries to train crews.

The accident occurred as train 2MP9 passed the southern end of the Mile End crossing loop. As it approached train 2MP1 under a ‘calling on/low speed’ signal, some stumpy vegetation and a low fence initially obscured the driver’s view of the empty flat wagons at the rear of the train. When the driver finally saw the rear of train 2MP1, he immediately made an emergency brake application, but was unable to stop the train before it collided with 2MP1.

While acknowledging the requirement under a ‘Proceed Restricted Authority’, for drivers to be able to stop their train within half of the distance that the line ahead is clear, the ATSB noted that the network control officer’s pathing of a train onto a line occupied by a preceding train (when an alternate route was available and not obstructed), had created an elevated level of risk. Similarly, well thought out and clear communications between the network control officer (NCO) and crew of the approaching train (as to the presence of another train on the line ahead) could have significantly enhanced the train crew’s situational awareness.

The Australian Rail Track Corporation (ARTC) and SCT Logistics have implemented a range of proactive strategies for enhancing the safe operation of train movements when entering an occupied section of track under a ‘Proceed restricted authority’ (PRA). This includes the use of all available infrastructure to reduce risk, encouraging communications between train drivers and NCOs where clarification of operational conditions is necessary, and a review of the National Train Communications System (NTCS) for the Adelaide area.

Safety message

Train drivers should carefully consider their obligations when accepting a ‘Calling on/Low speed’ signal indication in relation to sighting constraints, train speed and occupation of the track ahead. In circumstances where sighting constraints may exist, drivers should consider requesting further information from the NCO before moving through the track ahead.

When dispatching trains, NCOs should carefully consider the pathing of trains under their control and the communication of information that may mitigate collision risk. 

Read the final report: Collision between freight trains 2MP1 and 2MP9, Mile End, South Australia, on 31 March 2015

Low-flying accident

AO-2014-131_VH-TRS.jpg

A fatal wirestrike accident involving a Cessna 182L graphically illustrates the dangers of unauthorised low-level flying.

On 20 July 2014, the aircraft struck wires from a high voltage powerline while the pilot was conducting a private flight at low altitude near the rural township of Burrumbuttock, NSW.

Witnesses saw the aircraft flying low towards the township before it struck wires above a paddock on the outskirts of the town. The aircraft then rolled and impacted terrain. The wreckage came to rest a short distance from the Farmers Inn. Tragically, the pilot died in the accident.

The ATSB found no evidence of any engine or airframe defect that may have contributed to the accident.

Importantly, the pilot did not hold any approval to conduct low flying and had not received training to identify hazards or operating techniques for flight close to the ground. The evidence also indicated that the pilot had a history of unauthorised low flying.

The pilot was reported to be in good health with no issues that might have affected his ability to fly an aircraft. Despite this, the postmortem medical examination revealed a pre-existing medical condition that could have resulted in pilot incapacitation.

While it is possible the pilot may have been incapacitated immediately before the accident, the aircraft was flown at a level that provided little margin for error if an event had been experienced.  

Safety message

This fatal accident provides a clear message to pilots: don’t fly low if you’re not authorised, or don’t have to.

Flying below the regulated thresholds of 1,000 feet AGL overpopulated areas and 500 feet over non-populated areas provides very little margin for error if something goes wrong. Pilots who fly below this height without appropriate training and an operational reason to do so are exposing themselves and any passengers to an increased risk of striking hazards, such as electrical power lines, many of which are difficult to see from the cockpit of an aircraft in flight. 

Low-level flying is one of the ATSB’s top safety concerns for general aviation pilots. More information can be found on the ATSB’s SafetyWatch page or via the ATSB’s avoidable accident publication Low-level flying.  

Read the final report: Wire strike and impact with terrain involving a Cessna 182L, VH-TRS, Burrumbuttock, New South Wales, on 20 July 2014

In-flight engine shut down

AO-2013-172_Air-turbine-starter.jpg

The failure of an air turbine starter led to the in-flight shutdown of the number one engine of a China Airlines Airbus A330 aircraft in October 2013. (An air turbine starter uses pressurised air to rotate the high-pressure rotor within the engine during the engine start sequence).

The incident occurred approximately four hours into a flight from Sydney to Taipei, Taiwan ROC. The flight crew completed a precautionary shutdown of the number one engine in response to a low oil pressure warning, and diverted the flight to Cairns, Queensland.

The ATSB investigation found that the air turbine starter had sustained an uncontained failure. When the starter failed, an oil scavenge pipe from the number one engine was severed by debris that had not been contained by the starter casing. This resulted in a rapid loss of oil that required the number one engine to be shutdown.

The investigation identified that the starter failure was due to the failure of the output shaft bearing. Damage to the bearing was consistent with exposure to transient loads from the crash engagement of the starter clutch during engine starts, or, from axial loads to the bearing from the horizontal driveshaft.

Safety actions taken

To eliminate the potential for crash engagements to occur during operation of the air turbine starter, the starter manufacturer was phasing out the single pawl and ratchet clutch mechanism. A redesigned air starter using a full range pawl and ratchet is being incorporated into service. The manufacturer has also initiated changes to limit the potential for axial loads to be applied to the output shaft bearing of the turbine stater.

The resulting changes in design will eliminate air turbine starter failures associated with crash engagements, though they will not completely eliminate the potential for failures to occur (contained or otherwise).

Other safety action from the starter manufacturer, the engine manufacturer, and the operator includes a number of changes to the procedures for oil level checks and changes.

The ATSB is satisfied that the likely reoccurrence of this failure mode will remain low as a result of these safety actions.

Read the final report: Engine shut down in-flight involving Airbus A330-302, B-18358, 887 km east-north-east of Darwin Airport, on 3 October 2013

Passenger train hits equipment

RO-2015-003_Montgomery.jpg

A V/Line passenger train was brought to a grinding halt after it collided with maintenance equipment left behind from track work.

On 16 February 2015, track maintenance was being conducted at Montgomery (between Sale and Bairnsdale) in Victoria. To allow a passenger train to pass through the section, the maintenance gang cleared the track and lifted the track protection. When the gang vacated the line however, some equipment was left behind on the track. 

As the V/Line passenger train approached the work site, the driver saw the obstruction. Despite making an emergency brake application the driver was unable to bring the train to a stop before it collided with the equipment. The train remained on the track and there were no injuries to passengers or rail personnel.

The ATSB’s investigation found that the item of maintenance equipment struck had earlier been moved along the track - away from the immediate area of works. Subsequently, this equipment was overlooked when the track was cleared of workers and other tools.

The task of ensuring that the line was clear had cascaded to a third party within the maintenance gang. There was no formal system in place to manage this process of informal delegation.

As a result of this and other related safe working incidents, V/Line has advised that a review of infrastructure rules, safety procedures and training has been implemented.

Safety message

This incident highlights the need for track maintenance personnel to be particularly vigilant in ensuring that no obstructions remain on the line when authorising the passage of a train through a work site.

Similarly, network managers should ensure that systems and processes are in place to minimise the potential for maintenance equipment to be left on track. 

Read the final report: Passenger train collision with maintenance equipment, Montgomery, near Sale, Victoria, on 16 February 2015

Ballooning tragedy

AO-2013-116_Kavanagh.jpg

A tragic ballooning accident in the Northern Territory shows how quickly clothing entanglement in industrial equipment can cause a fatality.

On 13 July 2013 a Kavanagh E‑260 balloon was being prepared for a charter tourist flight near Alice Springs, Northern Territory. Due to the wind conditions at the time, the passengers were pre-loaded into the balloon basket as it lay on its side. As one of the passengers prepared to enter the basket, their scarf became entangled in a fan that was being used to inflate the balloon envelope. Consequently, the passenger was rapidly drawn into contact with the fan’s steel guard and the scarf was pulled tightly around their neck. Despite being provided with first aid, and subsequent medical treatment, the passenger died as a result of their injuries several days later.

The ATSB found that pre-loading of the passengers during the inflation process, although appropriate in the wind conditions, resulted in them coming into close proximity to the operating inflation fan. Additionally, the mesh and steel tubing guard positioned around the inflation fan was ineffective in preventing loose items of clothing from becoming entangled in the wooden fan blades and driveshaft. As a result, when the passenger approached the balloon basket in preparation for loading, their scarf was drawn into the fan blades, leading to fatal injuries.

The pilot conducted two safety briefings prior to the proposed flight that advised the passengers to remain clear of the fan as it was noisy and dangerous. A warning sign fitted to the fan was also pointed out. However, none of the passengers recalled that the specific danger of fan entanglement had been mentioned.

Shortly after this accident, the ATSB forwarded a Safety Advisory Notice (SAN) to balloon operators highlighting the circumstances of this occurrence and advising that they review their risk controls in relation to the safety of inflation fans. With the assistance of the Professional Balloon Association of Australia and the Australian Ballooning Federation (ABF) the SAN was also provided to their members. The ABF and Northern Territory (NT) WorkSafe also issued safety alerts highlighting the danger of fan entanglement.

The balloon operator made a number of changes to prevent a similar accident, including:

  • modification of all fan guards to reduce the likelihood of entanglement
  • establishment of a passenger exclusion zone in the vicinity of the fan
  • assignment of a crew member whose sole duty was to operate and supervise the fan
  • inclusion of detail on the danger of entanglement in the passenger briefing card.

Safety message

This accident highlights how quickly entanglement in industrial equipment, such as the inflation fan, can cause fatal injury. While highlighting the danger to those unfamiliar can reduce the risk, isolating the hazard through effective fan safeguarding and passenger control is the most effective method of preventing such tragic accidents.

Read the final report: Flight preparation event involving Kavanagh Balloons E-260, VH-FSR, near Alice Springs Airport, Northern Territory, on 13 July 2013