Collision after partial power loss

AO2015036_news.jpg

A light aircraft collision between a Piper PA-28 and Cessna 172 shows why it’s crucial to manage and respond to partial power loss immediately. 

Summary

On 11 April 2015, a Piper PA-28 aircraft suffered engine problems after take-off and the student pilot attempted to return immediately to Moorabbin Airport.   As the Piper landed, it touched down about one third of the way along the runway. The pilot attempted to slow the aircraft, and its left wing collided with the tail of a Cessna 172 aircraft, which was waiting on an adjacent taxiway.

The pilot of the Piper was not injured but the pilot and passengers of the Cessna were treated for minor injuries. Both aircraft sustained substantial damage.

The incident was a good example of how quickly things happen; about 90 seconds after an aircraft took off it was back on the ground and at least two aircraft had to be sent around in the interim.

The ATSB advises that a pre-flight safety brief that considers actions to take following a partial power loss after take-off, will give pilots a much better chance of maintaining control of their aircraft and of responding immediately. The ATSB publication Avoidable Accidents No. 3 – Managing partial power loss after take-off in single-engine aircraft gives more information to pilots.

Incident in detail

On 11 April 2015, the student pilot of a Piper PA-28 aircraft, registered VH-TXH, taxied at Moorabbin Airport, Victoria, for a solo flight to the local training area. At about 1136 Eastern Standard Time, the aerodrome controller – east, cleared the Piper for take-off.

At about 1137, the pilot of a Cessna 172 aircraft, registered VH-EUU, contacted the surface movement controller and requested a clearance to taxi for a local private flight, with three passengers on board. The surface movement controller cleared the Cessna to taxi to runway 35R via taxiway A, and the pilot began taxiing.

The pilot of the Piper reported that the take-off run was normal, but after rotation, the engine intermittently ran roughly, and then regained full power. At about 1138, the pilot advised the aerodrome controller - east of engine trouble and requested a return to land. The controller observed that the Piper did not appear to be climbing out normally and was then quite low, and offered the pilot runways 22 or 31 if required. The pilot elected to use runway 22.

The aerodrome controller – east advised the surface movement controller and the aerodrome controller – west of an aircraft with engine trouble, and coordinated with the surface movement controller for runway 22. At about 1139, the aerodrome controller – east cleared the Piper to land. The pilot of the Cessna conducted a tight right turn towards runway 22 and the aircraft touched down about one third of the way along the runway. The aerodrome controller – east and the surface movement controller observed that the Piper appeared to be travelling too fast to stop before the end of the sealed runway.

The pilot of the Piper assessed that he was not going to be able to stop the aircraft before the end of the sealed runway, but that there was a suitable grassed overshoot area beyond. The aerodrome controller – west was standing up, sighted the Cessna on taxiway A, and alerted the surface movement controller. As the Piper approached the end of runway 22, the pilot sighted the Cessna on taxiway A to his right, and veered to the right in an attempt to pass behind the Cessna. The surface movement controller directed the Cessna to stop. The pilot of the Cessna braked immediately and sighted the Piper, but assessed that if he stopped there, the Piper would collide squarely with the Cessna, so he released the brakes and progressed forwards. The left wing of the Piper then collided with the tail of the Cessna.

The pilot of the Piper was not injured. The pilot and passengers of the Cessna were treated for minor injuries. Both aircraft sustained substantial damage.

A post-accident inspection of the Piper’s engine found a small quantity of oil on the cylinders and some fouling of the spark plugs which may have led to the rough running.

Safety message

The ATSB publication Avoidable Accidents No. 3 – Managing partial power loss after take-off in single-engine aircraft, found causes of partial power loss after take-off include fuel starvation, spark plug fouling, carburettor icing and pre-ignition conditions. A pre-flight safety brief that considers actions to take following a partial power loss after take-off, gives pilots a much better chance of maintaining control of the aircraft and of responding immediately. Such actions include landing immediately within the aerodrome, landing beyond the aerodrome, and conducting a turn back towards the aerodrome.

Read the final report: Collision on the ground involving a Piper PA-28, VH-TXH, and a Cessna 172, VH-EUU, Moorabbin Airport, Victoria, on 11 April 2015

Reducing helicopter fires

R44_BulliTops_AO2013055.jpg

A fatal Robinson R44 helicopter accident has prompted the ATSB to recommend safety improvements to helicopter fuel tanks in the United States and Europe.

Four people died in the March 2013 accident at Bulli Tops in New South Wales. The R44 helicopter they were travelling in was engulfed in fire after striking a tree and hitting the ground.

Following this accident, Australia's Civil Aviation Safety Authority, and other international regulators, made it mandatory for R44 helicopter operators to replace the R44's all-aluminium fuel tank with a bladder-type fuel tank.

ATSB Chief Commissioner Martin Dolan said that bladder-type fuel tanks reduce the risk of post‑impact fire in the R44. But the ATSB remains concerned at the risk of post-impact fire in helicopters not fitted with crash-resistant fuel systems.

'We believe the US Federal Aviation Administration (FAA) and the European Aviation Safety Agency (EASA) can help improve the safety of many helicopter pilots and their passengers,' Mr Dolan said.

'We have issued safety recommendations to the FAA and EASA. We ask them to take action to increase the number of crash-resistant fuel systems fitted to existing and newly-manufactured helicopters.

'Under international convention, we would expect to hear from the FAA and EASA about their proposed responses to these recommendations by early September 2015,' Mr Dolan said.

The Bulli Tops accident was similar to other R44 accidents involving fatal post-impact fire that made survivability impossible. In each case, the R44s were fitted with all-aluminium fuel tanks.

Mr Dolan said, 'Statistical analysis of accidents in Australia and the United States over ten years found a higher proportion of post-impact fires involving R44s than for other similar helicopter types.'

The analysis also identified that, despite a 20-year-old requirement for new helicopters to have a crash-resistant fuel system, several helicopter types are being made without such a system. In addition, although modification kits are available for a number of helicopter types, they have not been incorporated in many of the existing civil helicopter fleet.

Read the final report: Collision with terrain involving Robinson R44 helicopter, VH-HWQ, at Bulli Tops, near Wollongong, New South Wales, on 21 March 2013

Antarctic exposes risks

Antartic_news.jpg

Flying visually in poor visibility continues to be a major aviation concern, following a serious helicopter accident injuring three people in Antarctica on 1 December 2013.

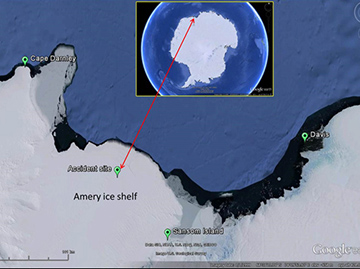
An ATSB investigation into the accident found that an Aérospatiale AS350B2 helicopter, in company with a second helicopter, was on a return flight to Davis Base, Antarctica after supporting a scientific task at a penguin rookery at Cape Darnley. The helicopters refuelled at a fuel cache on the Amery Ice shelf before flying south-east to their next refuelling stop.

Between 1993 and 2013 there were 11 accidents involving inadvertent visual flight into 'instrument meteorological conditions', such as poor weather or cloud.

The ATSB concluded that, as a result of changing weather with a rapid reduction in visual cues, and a breakdown in the pilot's scan of his flight instruments, the pilot probably became spatially disoriented while executing a right turn. The pilot was attempting to return to the previous landing site to wait until the weather improved.

ATSB Chief Commissioner Martin Dolan, said this accident serves as yet another reminder how weather can change very quickly and turn a routine flight into a tragic accident in poor visibility conditions. This is particularly the case in Antarctica.

Mr Dolan said, "Between 1993 and 2013 there were 11 accidents involving inadvertent visual flight into 'instrument meteorological conditions', such as poor weather or cloud".

"In forecast marginal weather, while alternative options such as diverting or turning back are part of the solution, pilot training and the appropriateness of the aircraft's instrumentation must also be considered."

"Pressing on into poor visibility conditions carries a significant risk of severe spatial disorientation due to powerful and misleading orientation sensations," said Mr Dolan.

Following this accident the operator introduced new helicopters with an autopilot to reduce pilot workload. They also introduced simulator training by an experienced Antarctic pilot, a situation awareness course, and training on the limitations of the radar altimeter. The operator also provides decision-making guidance for early avoidance of unexpected white-out conditions.

Read the final report: Collision with terrain involving an Aérospatiale Squirrel helicopter, AS350B2, VH-HRQ, 240 km west of Davis Base, Antarctica, on 1 December 2013

SafetyWatch: Flying with reduced visual cues

Our investigators

When responding to accidents and serious incidents, investigators with a wide range of skills and qualifications are deployed in teams to carry out the investigation and discover what went wrong.

Most investigations (other than short investigations) involve deployment of a small team to the incident site to study the damaged or destroyed transport vehicle and other physical evidence at the site. The team also conducts initial interviews with survivors, witnesses, and people such as the operator and maintenance staff and family of the crew and passengers. Investigators will deploy to the site as soon as possible to avoid any loss of evidence that can occur over time, and also to allow quick clearance of accident sites.

The team will conduct checks on maintenance of the transport vehicle and material from the site may be brought to the ATSB’s technical facilities in Canberra for close study and technical analysis.

ATSB transport safety investigators have a wide range of skills and qualifications. Many of our investigators have had careers in the transport or defence industries before joining the ATSB. Among their number are pilots, air traffic controllers, psychologists, master mariners, train drivers engineers—from many disciplines including materials, electronics, avionics, rail, marine, aeronautical, and mechanical. In recent years we have also recruited graduates directly from university.

Many vehicles are fitted with data recorders, similar to the ‘black boxes’ that people associate with aircraft.  Voyage data recorders on marine vessels, cockpit voice recordings, flight data recorders as well as train loggers, may provide data which will be downloaded and analysed using specialised equipment and processes in the ATSB’s technical facilities. Often, other electronic evidence is gathered from electronic chips in vehicle systems and components—these devices can reveal much about the performance of a transport vehicle and its systems in the period leading up to the accident. Investigators will also gather devices such as GPS units, tablet computers and smart phones found in wreckage, which can provide valuable information such as the route taken. Air-traffic control data and in-port vessel management systems are valuable sources of data that often reveal movement leading up to an incident.

Where necessary, investigators will collaborate with academics and international specialists when additional expertise or advice is required.

In the office, the team will compile their evidence, conduct a thorough analysis and form conclusions about what might have led to the occurrence. A formal report is written and initially released to the directly involved parties, who are given the chance to comment on the factual accuracy of the report before it is completed. The final report is then approved by the Commission and formally published.

Published reports are available from www.atsb.gov.au

Fire on freight train

  • Fire on freight train illustrates why it’s vital that dangerous goods are packed in accordance with relevant requirements.
FireDamagedFreight.jpg

At about 1055 on 21 August 2014, train 3DA2, carrying containerised freight (including dangerous goods), arrived at Snowtown, South Australia. While at Snowtown, the crew noticed smoke coming from one of the containers conveying dangerous goods. The crew contacted ARTC Network Control to arrange for the Country Fire Service to attend the site. An exclusion zone was set up around the site and the fire was brought under control with minimal damage sustained.

The ATSB found that freight within the affected container, including undeclared dangerous goods, had been packed in a manner that was not in accordance with the code of practice for Transport of Dangerous Goods by Road or Rail, or the Genesee & Wyoming Australia dangerous goods policy.

Incident illustrates the importance of freight forwarders and rail operators ensuring that dangerous goods freight accepted for carriage meets the relevant requirements of the Transport of Dangerous Goods by Road or Rail code of practice.

Genesee & Wyoming Australia had a documented policy on the transportation of dangerous goods, including a Standard Condition of Carriage, which documented the obligations of GWA’s customers when providing freight for transportation. However, GWA had no active verification processes in place to check and confirm compliance with those requirements (either in total or in part through random selection). Such a process may have provided the opportunity to detect any undeclared dangerous goods or inappropriately packed freight before an incident or accident resulted.

GWA has undertaken an independent audit of their policies and procedures for consigning freight, including the adequacy of training in receiving handling and storage of dangerous goods. GWA has also undertaken to improve communications with customers at their Alice Springs and Darwin terminals – to identify where deficiencies may exist and how they might be best addressed.

Safety message

This incident illustrates the importance of freight forwarders and rail operators ensuring that dangerous goods freight accepted for carriage meets the relevant requirements of the Transport of Dangerous Goods by Road or Rail code of practice. All rail operators should ensure that their policies and procedures for the acceptance of dangerous goods are effective in ensuring that the goods accepted have been appropriately packed to minimise the risk of incidents during transportation.

Read the final report: Fire on freight train 3DA2, near Snowtown, South Australia, on 21 August 2014

Seek ATC services if unsure

  • ATSB investigation into a Cessna 172 accident encourages pilots, unsure of their position or requiring navigational assistance, to seek Flight Following services from ATC.
  • Pilots are also encouraged to regularly practise the skills required to make a safe precautionary landing.
AO-2014-173_news.jpg

On 27 October 2014, at about 1030 EDT, the pilot of a Cessna 172 aircraft, departed Ballarat, Victoria, for Luskintyre, NSW, on a private flight under the visual flight rules. The pilot had planned the flight carefully, and although he had adequate fuel to reach Luskintyre without refuelling, he planned to reconsider his progress at Temora, NSW, and land for additional fuel if required.

The pilot encountered some poor weather during the early stages of the flight and, although it was unplanned, he elected to land at Wangaratta, Victoria, to take a break and have some refreshments. While at Wangaratta, he also took the opportunity to add some fuel. After a short break and refuel, the pilot continued to Temora, where he elected to land for another break. The pilot re-assessed his fuel requirements at Temora, and determined that he had sufficient fuel to continue to Luskintyre with ample reserve without refuelling.

After departing Temora, the pilot planned to overfly Rylestone, Denman and Jerrys Plains, en route to Luskintyre. The flight proceeded as planned to about Kandos (just south of Rylestone), where the pilot visually fixed his position. At that point, rather than continuing as planned overhead Rylestone then on to Denman, the pilot elected to track directly to Luskintyre.

The direct track between Kandos and Luskintyre was over heavily treed and undulating terrain, leaving the pilot unable to positively visually fix his position. As he continued in an easterly direction, the pilot grew increasingly concerned about the possibility of infringing controlled airspace further to the east. Conditions at the time were windy and although the pilot recalled that the visibility was good, there may have been some bushfire smoke in the area.

Rather than risk infringing controlled airspace, the pilot decided to make a precautionary landing to ascertain his position. He located a valley that appeared to have some cleared areas, then circled for several minutes assessing precautionary landing options. The pilot commented that precautionary landing options were very limited, but he ultimately selected a paddock that was clear of obstacles, and while relatively short, it offered an uphill landing run to assist in stopping the aircraft.

During his approach to land on the selected paddock, with full flap selected, the pilot found himself overshooting the selected aim point. He endeavoured to recover the profile, but had increasing difficulty maintaining the preferred aim point. Concerned that he would not be able to land safely, the pilot elected to discontinue the approach and commenced a go-around. As the go-around proceeded however, the pilot found that he was unable to climb over tress ahead of the aircraft on rising terrain beyond the far end of the selected paddock. He was able to manoeuvre around a small number of individual trees, but collided with a line of trees, slightly further on. The aircraft was substantially damaged in the collision and the pilot received serious injuries.

The aircraft was fitted with an emergency locator transmitter (ELT) which was activated by the impact. An overflying aircraft detected the ELT signal at about 1715 EDT, and search and rescue authorities were alerted. Sometime after the accident, the pilot was also able to activate a portable locator beacon. In addition, the pilot had left a Flight Note at the point of departure. When the pilot had not made contact by the nominated time, the holder of the Flight Note commenced enquiries and notified authorities.
The aircraft wreckage was ultimately discovered by a local resident, around 2 hours after the accident, independent of other search and rescue activities. The local resident alerted authorities, who attended the scene and were able to secure the wreckage and provide medical assistance to the injured pilot.

Safety message

In many cases, deviation from a flight plan is necessary to ensure continued safe flight. Where deviation from a flight plan is not essential, pilots are encouraged to consider the risk of operational complications such as potential difficulties with navigation or fuel management. Deviation from a flight plan or Flight Note may also affect search and rescue activities in the event of an accident, to the extent that a search is conducted in the wrong place.

Where available, pilots unsure of their position or requiring navigational assistance, are encouraged to seek Flight Following services from ATC. In this case, contact with ATC may have allayed the pilot’s concerns about the prospect of infringing controlled airspace, and negated the need to consider a precautionary landing. A fact sheet regarding Flight Following services is available on the Airservices Australia website via the following link, under the group heading working with air traffic control.

With respect to precautionary landings, pilots are encouraged to initiate an early go-around as soon as there is any doubt regarding the prospects of a safe landing. The potential for a safe go-around may diminish as an aircraft continues an approach, particularly where there is rising terrain or obstacles beyond the selected precautionary landing area.

...pilot's, unsure of their position or requiring navigational assistance encouraged, to seek Flight Following services from ATC.

While in this case the aircraft was found by a local resident independent of search and rescue activities, the accident nonetheless provides a reminder of the potential value of a Flight Note. Pilots are encouraged to prepare a Flight Note where relevant, and to ensure that the information provided on the Flight Note is as accurate as possible. Pilots are also encouraged to advise ATC of any deviation from the planned route, to ensure that search and rescue authorities have access to updated information where relevant.

Read the final report: Collision with terrain involving a Cessna 172, VH-ZZD, near Putty, New South Wales, on 27 October 2014

Additional reading:

Powerlines may be invisible to the naked eye

Wirestrike_ao2014153_news.jpg

On 20 September 2014, the pilot of a Piper PA-25 aircraft, conducted a ferry flight from Camden to Bunyan aeroplane landing area, via Goulburn, New South Wales.

After refuelling at Goulburn aerodrome, the pilot tracked to overhead Michelago and continued south towards Bunyan. About 10 km south of Michelago, the pilot intended to overfly a private airstrip to assess its condition and suitability as a potential out-landing site for gliders operating from Bunyan.

The aircraft was heading south and as the airstrip was oriented approximately north-south, the pilot elected to overfly the runway. When about 300 m beyond the runway threshold, the aircraft struck powerlines that crossed the runway about 15 m above ground level, dislodging the windscreen and canopy. The top of the fin was severed by the powerlines. Immediately after the strike, the aircraft banked to the left before returning to level flight. The pilot assessed that the aircraft was too high to land ahead on the remaining runway and made a right turn, initially planning to land towards the north on the adjacent paddock. However, due to the rough surface of the paddock and tailwind, he conducted a short downwind leg before turning to the right, and the aircraft landed into wind on the runway.

The top of the fin was severed by the powerlines.

The ability of pilots to detect powerlines depends on the physical characteristics of the powerline and the effect of weather conditions. Powerlines may be invisible to the naked eye. When flying at low altitude, pilots should use additional cues to identify powerlines, such as the power poles and buildings to which the powerlines may connect.

Safety message

Research conducted by the ATSB found that 166 aircraft wirestrikes were reported to the ATSB between July 2003 and mid-June 2011 and another 101 occurred and were unreported but identified by electricity distribution and transmission companies. The majority of wirestrike occurrences were associated with aerial agriculture operations however, 22 occurrences (8 per cent) involved private operations. See the research report AR-2011-004: Under reporting of aviation wirestrikes.

Depending on the environmental conditions, powerlines may not be contrasted against the surrounding environment. Often the wires will blend into the background vegetation and cannot be recognised. In addition, the wire itself can be beyond the resolving power of the eye: that is, the size of the wire and limitations of the eye can mean that it is actually impossible to see the wire. As such, pilots are taught to use additional cues to identify powerlines, such as the associated clearings or easements in trees or fields that can underlie the powerline, or the power poles and buildings to which the powerlines may connect.

The ATSB publication, Avoidable Accidents No. 2 – Wirestrikes involving known wires: A manageable aerial agriculture hazard, advises pilots to always conduct an aerial reconnaissance to confirm wire locations and other hazards.

Risks associated with operations to private airstrips can be mitigated by ALA owners assessing their airstrips against the guidance in CAAP 92-1(1) Guidelines for aeroplane landing areas. Such risk assessments would benefit from giving consideration to first time users of the ALA.

Safe flight depends on power

Cessna206_VH-KRR_news.jpg

The pilot of a Cessna 206 aircraft conducted a solo training flight from Bankstown to Cootamundra, New South Wales and return. At about 0800 Australian Eastern Daylight Time, the aircraft departed Bankstown Airport with full fuel and landed at Cootamundra Airport at about 0943.

After taxiing to the parking bay and shutting down the engine, the pilot dipped the fuel tanks. He reported that 100 litres remained in the right tank and 85 litres in the left. This indicated an actual fuel consumption rate of about 67-70 litres/hour, and about 12 litres less fuel remaining in the tanks than the pilot had expected.

...about 7 litres of fuel (unusable) remained in the right tank and none in the left.

At about 1022, the aircraft departed Cootamundra on a planned track to Bankstown via Rugby and Bindook. At about 1100, the pilot observed that the aircraft had deviated from the planned track and attempted to track direct to Bindook, however took up a heading of about 120°, which resulted in a further deviation from the planned track.

At about 1114, and at 5,500 feet above ground level, the aircraft’s engine surged and then stopped. The pilot conducted some emergency checks and sighted a suitable landing area. The aircraft collided with trees about 50 metres short of the intended landing site and was substantially damaged. The pilot sustained a minor injury.

The aircraft owners attended the accident site and reported that about 7 litres of fuel (unusable) remained in the right tank and none in the left. This incident highlights the importance of thorough pre-flight planning and monitoring and reassessing actual versus planned flight tracks and aircraft fuel consumption.

Read the final report: Collision with terrain involving a Cessna 206, VH-KRR, 33 km west of Nowra Airport, New South Wales, on 16 October 2014

Read more about: Starved and exhausted: Fuel management aviation accidents

Tragedy prompts low-flying warning

An aircraft accident that resulted in the fatality of a child passenger is a shocking reminder to all pilots about the dangers of unauthorised and unnecessary low-level flying, according to the ATSB.

The accident occurred on 12 April 2014 when a Maule M-5 aircraft, with a pilot and two passengers on board, struck a powerline across the Clarence River in New South Wales. The aircraft then collided with water, coming to rest inverted with the cabin submerged.

The pilot and front-seat adult passenger escaped the cockpit through one of the forward doors and attempted to free the rear-seat child passenger from the flooded cabin. After repeated attempts by the pilot to open the rear-right cabin door, the rear-seat passenger was recovered through a cockpit door. Sustained attempts to resuscitate the rear-seat passenger were unsuccessful.

The ATSB found that the accident was an unintended consequence of the pilot’s spur-of-the-moment decision to fly at a very low level along the river, in an unfamiliar environment and below the minimum stipulated height for flights over unpopulated areas.

The pilot reported seeing the powerline just before the collision, but with insufficient time to avoid a wirestrike. The pilot was not approved to conduct low-flying operations and had not completed any training to identify the hazards associated with such operations.

ATSB general manager of strategic capability, Julian Walsh, said the accident is a very powerful and tragic reminder for pilots about the dangers of unauthorised and unnecessary low‑level flying.

“Flying at low heights—below 1,000ft above terrain for populous areas or 500ft for other areas—presents many obstacles and has very low margin for error,” Mr Walsh said. “Most private pilots generally have no reason to fly at these dangerous low levels and there are special training and endorsement to do so.”

“The tragic accident at Clarence River is just one of many accidents we’ve investigated that resulted from aircraft flying too low. This accident was completely avoidable. It should serve as a stark warning to other pilots who are ever tempted to fly lower than necessary.”

A copy of the investigation report (AO-2014-068) into this accident is available on the ATSB website. Low-level flying is one of the ATSB’s top safety concerns for general aviation pilots. More information can be found on the ATSB’s SafetyWatch page or via the ATSB’s avoidable accident publication Low-level flying.  

In-flight engine failure

AO2014098_EngineFailure_news.jpg

On 31 May 2014 at about 1322 Western Standard Time, a Beech Aircraft Corp D17-S, was being used to conduct a private flight from Crooked Brook landing area to Geraldton airport, Western Australia. The flight was conducted in visual meteorological conditions and the pilot was the only person on board.

After departure, the pilot tracked FNS in a northerly direction and climbed to an altitude of about 2,500 feet above mean sea level (AMSL). About a minute after setting the engine to cruise power, the pilot felt a violent vibration with an associated decrease in engine power. The pilot described the engine as ‘surging’ and ‘back-firing’. The pilot conducted initial troubleshooting and was unable to identify a reason for the engine malfunction. The vibration ceased and the engine was no longer producing power but the propeller was windmilling. The pilot elected to leave the landing gear retracted and set up a glide approach tracking to the north-east to locate a more suitable landing area to conduct a forced landing. A suitable paddock was identified that was near a house. The aircraft flew over a line of tall trees and then clipped a fence that was next to a private road leading to the house, went through a second fence on the other side of the road, which partially arrested the aircraft. It then impacted a large log and came to rest. A passer-by assisted the pilot to evacuate the aircraft. The pilot was seriously injured and transported to hospital and the aircraft was substantially damaged.

This accident is a timely reminder for pilots to consider the effect an in-flight engine failure at different altitudes has on the time available to manage that failure and identify a suitable forced landing area.

The pilot reported that he had conducted a pre-take-off brief covering the actions and considerations in relation to an engine failure. The pilot also indicated that he had flight planned to cruise at an altitude of 4,500 feet AMSL but amended this to 2,500 feet AMSL due to the increase in wind speed at altitude.

The pilot reported that the engine was subsequently examined and that a hole was located in the number five cylinder wall. Extensive internal damage was found and the reason for the internal engine failure could not be determined. The pilot indicated that the engine had failed at about 223 hours since it was last overhauled and that the specified time between engine overhauls was 1,000 hours.

Safety message

Pilots should consider the effect an in-flight engine failure at different altitudes has on the time available to manage that failure and identify a suitable forced landing area. In this instance the pilot had enough time to manoeuvre towards a different area.

The ATSB booklet Avoidable Accidents No. 3 - Managing partial power loss after take-off in single-engine aircraft contains information that is also relevant to a complete engine power loss.

The booklet highlights the importance of:

  • pre-flight decision making and planning for emergencies and abnormal situations for the particular aerodrome including a thorough pre-flight self-brief covering the different emergency scenarios.
  • conducting a thorough pre-flight and engine ground run to identify any issues that may lead to an engine failure.
  • taking positive action and maintaining aircraft control either when turning back to the aerodrome or conducting a forced landing until on the ground, while being aware of flare energy and aircraft stall speeds.

Read the final report: Engine failure involving a Beech Aircraft Corp D17-S, VH-FNS, 12 km east-south-east of Bunbury Airport, Western Australia, on 31 May 2014





