An axle bearing failure on a train wagon contributed to the derailment of a freight train near Hugh River in the Northern Territory on 23 December 2014.
The wagon, carrying distillate fuel, remained upright and there was some minor damage to the track (sleepers and rail clips). Fortunately, there were no injuries.
The ATSB found that the journal and bearing on the wagon seized and lost interference fit. This generated high levels of frictional heating between the bearing and axle journal, and the subsequent torsional shearing failure of the axle (a ‘screwed journal’). The axle failure immediately caused the leading axle of the trailing bogie to derail.
The ATSB concluded that a loss of lubrication or an internal bearing cage failure was the most likely contributor to the bearing breakdown and seizure. Evidence also suggested the breakdown developed relatively rapidly, given the absence of a positive fault detection from two bearing acoustic monitoring systems (RailBAM®) passed on the day of the occurrence.
Safety message
Bearing failures leading to derailment continue to occur within the Australian rail network. Rail operators must continue to be vigilant and ensure axle bearings, and in particular axle box type bearings, are correctly installed, maintained and monitored throughout their life.
On 15 January 2014, a Sydney Trains service made up of two four-carriage Tangara electric multiple units entered the underground section of the Eastern Suburbs Line under Sydney city centre heading towards its destination, Bondi Junction.
Some smoke and a burning smell were apparent emanating from the train at Central station and at all subsequent stations to Bondi Junction. A number of station and train crewing staff were aware of this but the condition was not reported to the appropriate network control officer as required under Sydney Trains’ Network Rules and Procedures.
The train terminated at Bondi Junction where a different driver took control of the train before it departed on its return journey. It then travelled to the next station, Edgecliff.
Shortly after departure from Edgecliff, at 1726, the lead bogie of the third carriage derailed due to a broken axle on the leading bogie of the third carriage. A piece of angle iron that became dislodged from the track infrastructure penetrated the floor of the third carriage and entered a space occupied by passengers. Fortunately, no passengers or train crew were injured.
The ATSB found that an unauthorised, non-standard repair had been carried out on the axle in December 1998 or January 1999 which introduced stress initiators, causing a crack to develop which over time propagated to the extent that the axle failed in service.
It was also determined that a number of organisational factors contributed to the incident. Poor communication and lack of adherence to procedures and reporting lines after the first problems were noticed, led to the train continuing in service and subsequently derailing.
Seven axles, including the failed axle, had been repaired in the same way. All were immediately located and removed from service.
Sydney Trains produced a number of safety recommendations which are being incorporated into their Safety Action Management procedures.
Safety message
Rail operators should ensure that maintenance procedures are followed and that non-standard repairs comply strictly with an approved variation and do not introduce new risks to operations.
Also, rail operators should review their internal training and communication pathways to ensure that critical communication can occur in line with best Rail Resource Management principles.
A recent aviation incident involving a student pilot and instructor shows why it’s essential to have a positive exchange of flight controls during flight training.
The incident occurred when the student pilot and instructor were doing crosswind circuit training in a Victa 115 Airtourer. As the aircraft flared to land, a strong gust of wind blew it off the runway centreline to the left, and the aircraft bounced hard.
The student initiated a go-around, applying full power, but the aircraft still drifted further to the left. As the aircraft was not climbing, the instructor called “taking over” and the student handed over control. The instructor lowered the nose of the aircraft to gain airspeed.
The aircraft continued to drift further away from the runway centreline.
The student noticed the flaps were in the down position and, thinking it would assist, and without checking with the instructor, retracted the flaps to the up position.
There should never be any doubt about who is flying the aircraft.
The aircraft descended and about 100 metres past the threshold of the runway, it collided with the airport perimeter fence. After a further 20 metres, the aircraft flipped over the fence and came to rest upside down. The instructor and student exited the aircraft quickly through the broken canopy, as fuel was gushing from the fuel tanks. Both received minor injuries, and the aircraft was substantially damaged.
Source: Aircraft operator
Safety message
It is important in flight training to have a positive exchange of flight controls. The US Federal Aviation Administration (FAA) has found that numerous accidents have occurred due to a lack of communication or misunderstanding regarding who had actual control of the aircraft, particularly between students and flight instructors. The FAA publication Aviation Instructor’s Handbook(Opens in a new tab/window), includes a section on the Positive Exchange of Flight Controls. The handbook provides guidance to use for the positive exchange of flight controls
On the morning of Saturday 5 October 2013, the pilot of a Rand Robinson KR-2 aircraft, registered VH-CTE, took off from an airstrip on private property 12 km west of Tumut, New South Wales. The pilot was reported to have intended flying to Holbrook, New South Wales, and return home the following evening.
When the pilot had not returned by early Sunday evening, authorities were notified. A search located the aircraft wreckage in the early morning on 7 October 2013. The wreckage was found about 450 m east-north-east of the departure airstrip. The pilot was fatally injured and the aircraft was destroyed by impact forces.
The pilot’s decision not to have proper maintenance performed on the aircraft most likely contributed to the ejection of the spark plug, resulting in the accident.
Data from a global positioning system receiver recovered from the wreckage identified that the pilot turned back towards the departure airstrip shortly after take-off. During the attempt to land back on the airstrip, the aircraft likely entered a stall. The pilot was unable to recover the aircraft before impacting terrain.
The ATSB’s examination of the wreckage found that a spark plug had been ejected from its respective cylinder head mount. The failure of the cylinder head spark plug mount was probably the result of an incorrectly installed thread insert. There were reports and evidence that the pilot maintained and modified the aircraft, despite not being qualified or authorised to do so. As well, in the previous 2 years, an authorised maintainer had not completed the required regular aircraft maintenance.
The pilot’s decision not to have proper maintenance performed on the aircraft most likely contributed to the ejection of the spark plug, resulting in the accident.
Safety message
Unauthorised maintenance increases the risk of mechanical failure. This, in turn, reduces the level of safety and increases the risk of injury or death.
Authorised aircraft maintenance is mandated to assure a level of safety for aircraft operations. That directive also identifies the requisite qualifications for the maintainer.
As well, managing airspeed and bank angle is critical to preventing an aerodynamic stall following partial engine failure after take-off. Research shows partial engine power loss is more complex and more frequent than a complete engine power loss. These accidents are typically a result of the aircraft entering an aerodynamic stall from a height where recovery is not possible.
A recent landing gear incident involving a Cessna 210 shows how as aircraft age, their original maintenance schedule may not be sufficient to ensure ongoing safety.
The Cessna 210, returning from a scenic flight with five passengers on board, was approaching to land at Kununurra Airport, Western Australia.
During the approach, the pilot selected the landing gear down but the landing gear down indicator light did not illuminate. The right and left main landing gear appeared to be down and locked but the pilot was unable to see the nose landing gear.
The pilot completed the relevant checklists and conducted a low-level pass over the runway so the aircraft’s operator could see from the ground if the landing gear was down.
As aircraft age, the original maintenance schedules may not be sufficient to ensure the aircraft’s ongoing safety.
The operator observed the landing gear and reported to the pilot that the landing gear appeared to be in the down position. The pilot returned for a landing on runway 12.
On landing, the main landing gear wheels touched down first. The pilot held full back pressure on the elevator controls to hold the nose wheel off the runway for as long as possible. After about 100 m, the nose of the aircraft sank on to the runway. At this point, the nose wheel collapsed, the propeller struck the runway, and the aircraft came to a stop. The pilot and five passengers were uninjured. The aircraft sustained minor damage, including damage to the propeller, nose wheel, and engine cowling.
The aircraft was last flown about three weeks before this incident, and the pilot reported that there was no outstanding maintenance.
This aircraft was manufactured in 1976 and, and at the time had 9,965 hours total time in service. The owner’s investigation into the incident determined that one of the nose landing gear down lock pins had failed. The pin failed in the area of the machined groove for the pin retention roll pin . The failed down lock pin migrated out and interfered with the nose landing gear actuator. This movement prevented the nose landing gear down lock mechanism from engaging in the down and locked position.
Failed nose landing gear downlock pin
Source: Aircraft owner
The Cessna nose landing gear downlock actuator pins have had a history of cracking and failing. In response, Cessna recommended the inspection of the pins to determine their safety.
Safety message
The incident highlights the importance of comprehensive, periodic maintenance inspections. It also shows the role manufacturers have in the continuing airworthiness instructions for maintaining ageing aircraft. As aircraft age, the original maintenance schedules may not be sufficient to ensure the aircraft’s ongoing safety. As a result of investigation report AO-2011-115 the ATSB encourages registration holders of class B aircraft to review their aircraft’s maintenance schedule to determine if it is the most appropriate for their aircraft and to ensure that it adequately provides for the continuing airworthiness of the aircraft.
In 2007, the ATSB released research report How Old is Too Old? The impact of ageing aircraft on aviation safety. The report found that some aircraft manufacturers have recognised that the original maintenance schedules may not be sufficient to ensure the aircraft’s (ongoing) safety. Those manufacturers have developed additional continuing airworthiness information.
As an aircraft ages up to and beyond its original design assumptions, the nominated maintenance program needs to be modified to take into account ageing issues. In particular, inspections of key areas or components not usually accessed.
CASA and Authorised Persons are obliged to take into account all relevant maintenance data or information pertinent to a particular aircraft type. This includes manufacturer’s data, Airworthiness Directives, Service Bulletins and other continuing airworthiness information.
CASA Maintenance Schedule 5 was originally conceived as a minimum schedule of maintenance activities, to be undertaken on a very limited range of relatively simple, ‘orphan’ aircraft
CASA Maintenance Schedule 5 was not originally intended to address ageing aircraft related issues. The literal application of this schedule on its own was not intended to replace the manufacturer’s instructions for continued airworthiness, where available.
The adequate maintenance of ageing aircraft requires the participation and ongoing cooperation of aircraft manufacturers, regulatory authorities, owners, operators, and maintainers.
Runway incursions are an ongoing safety concern at airports. This incident shows just how easily they can happen, even while following procedures and carrying out routine duties.
The incident occurred shortly after an ATR 72 aircraft, operated by Virgin Australia Regional Airlines, broadcast on the common traffic advisory frequency (CTAF), that they ‘should be turning straight in for a landing runway 16’.
At about the same time, the aerodrome reporting officer (ARO) was asked by airport ground staff to conduct a runway inspection, following a birdstrike report of another aircraft that just landed. He entered a safety vehicle, which was fitted with a flashing orange beacon, and then drove to the holding point for runway 16/34.
The ARO broadcast on the CTAF advising that the vehicle was preparing to enter the runway for a runway inspection. The ARO heard a beep-back, confirming that he had made the call on the correct frequency, but no other response was heard on the CTAF.
...the ARO heard ‘car vacate’ broadcast on the CTAF and sighted the aircraft landing on the far end of the runway in the rear-view mirror of the vehicle.
The CTAF broadcasts an automatic voice-back response if no calls have been made on the frequency for five minutes; otherwise a beep-back is broadcast. The ARO assumed that he received a beep-back rather than a voice-back, due to the calls made by the crew of the aircraft that had just landed.
He then conducted a thorough lookout for aircraft approaching and did not sight any. The ARO broadcast that he was entering the runway and commenced driving north along the runway. When at the northern threshold, the vehicle turned and drove south along the runway with no evidence of a birdstrike found.
The crew of the ATR 72 did not hear either broadcast from the ARO. The aircraft was in cloud during the approach, with the cloud base at about 2,600 feet and encountered some turbulence on final, with a crosswind of about 12 kt. The captain looked up out of the cockpit along the runway and sighted the safety vehicle on the white runway aiming point markings near the far end of the runway and immediately broadcast ‘car vacate’. (The first officer sighted the orange beacon when at about 10 feet AGL, but was not immediately aware that it indicated the presence of a vehicle on the runway).
When about 100 m from the southern end of the runway, facing south, the ARO heard ‘car vacate’ broadcast on the CTAF and sighted the aircraft landing on the far end of the runway in the rear-view mirror of the vehicle.
The ARO immediately drove the vehicle off the runway and once clear, broadcast that the safety vehicle had now vacated all runways.
The ARO had a handheld VHF radio and a VHF radio was fitted in the safety vehicle. When in the vehicle, the ARO switched off the handheld radio to avoid interference with the fitted radio. The ARO could alternatively be contacted via mobile phone. The ARO also had a UHF radio which was used to communicate with aerodrome ground staff. All normal communications between flight crew and the ARO are on the CTAF via VHF radio. The ARO reported that inside the terminal building there was a ‘black spot’ for VHF reception.
The ATSB was provided with the CTAF recordings. Both of the broadcasts made by the ARO included the standard phraseology of prefixing and suffixing each call with ‘Traffic Moranbah’ to alert aircraft to the location of the caller.
The ATSB’s investigation found that the ARO was in the airport compound for the duration of the calls broadcast at 25 NM, 10 NM and overhead by the aircraft. This meant he was not aware the aircraft was in the vicinity. The recording of the CTAF obtained by the ATSB verified all calls made by the crew of the aircraft and the ARO. The ARO calls were audible but less clear than the aircraft calls; however it could not be determined why the crew of the aircraft did not hear the ARO broadcasts. There was no requirement for the ARO to maintain a continuous listening watch on the CTAF. Six minutes elapsed between the broadcast from the captain of the aircraft overhead the aerodrome, to the call to the car to vacate.
Safety around non-controlled aerodromes is one of the ATSB’s major safety priorities. Research conducted by the ATSB found that, between 2003 and 2008, 32 runway incursions were recorded at non-controlled aerodromes. Broadcasting on and monitoring of the CTAF is the key way for pilots to establish situational and traffic awareness. The ATSB Limitations of the see-and-avoid principle study found that the effectiveness of a search for other traffic is eight times greater when a radio is used effectively in combination with a visual lookout, than when no radio is used. A pilot's guide to staying safe in the vicinity of non-controlled aerodromes is also a good source of information.
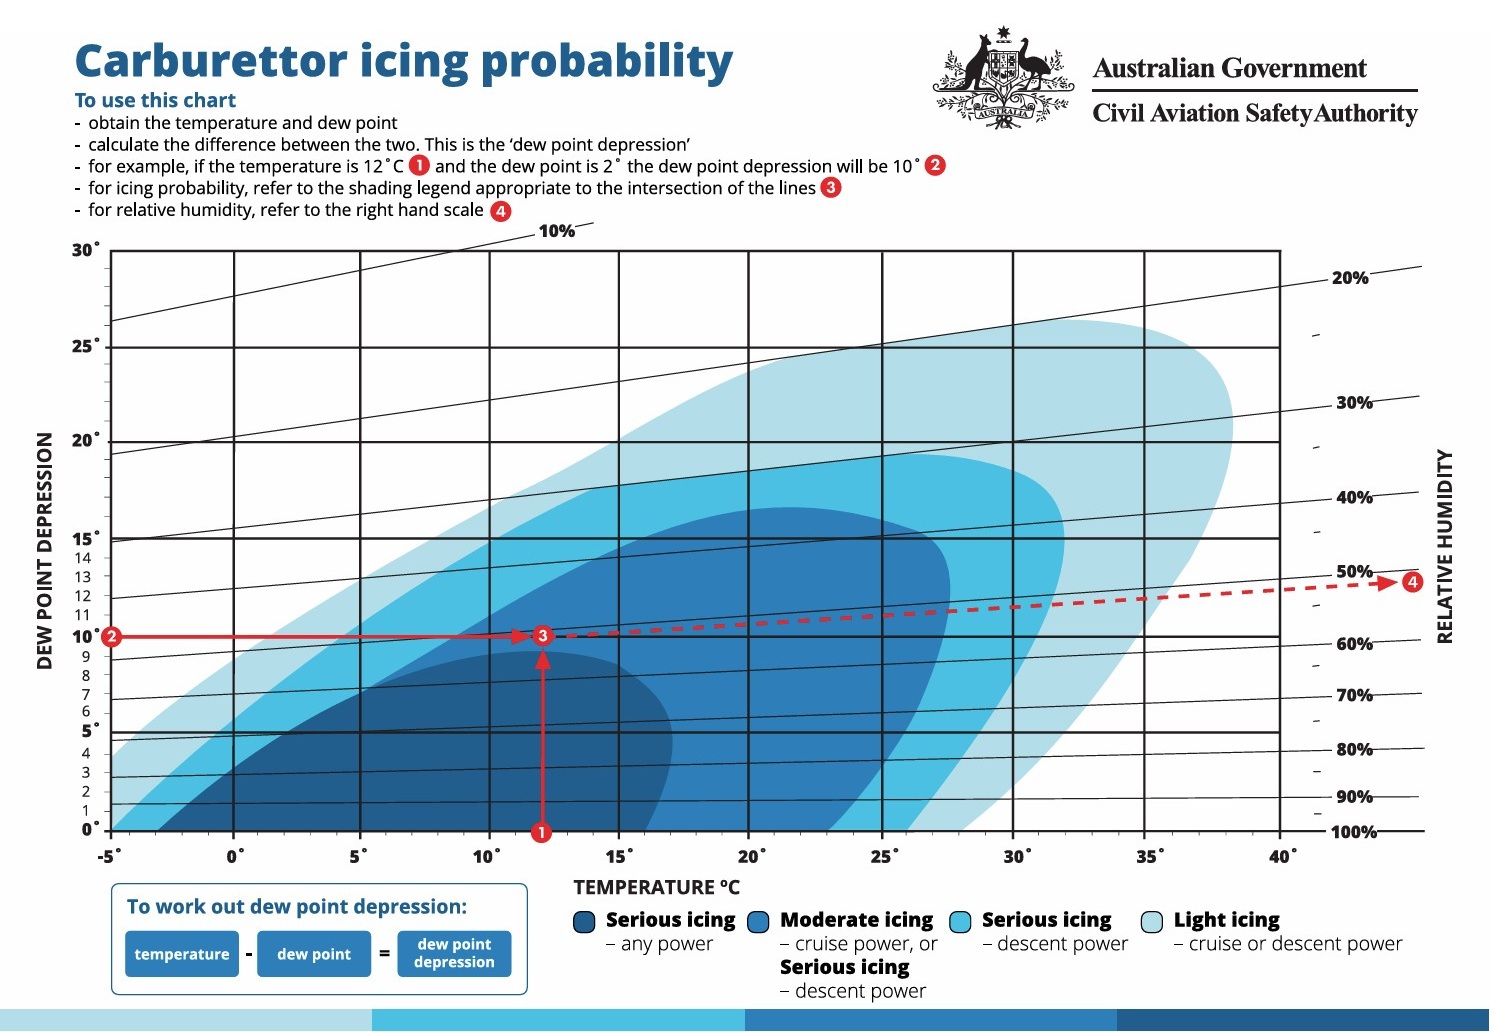
Carburettor icing can happen at temperatures of up to 38 degrees Celsius.
Carburettor heat should be applied immediately when an engine runs roughly.
Carburettor icing can occur even in relatively warm conditions - the higher the humidity, the more likely it is that ice will form in the air-intake system.
Carburettor icing likely contributed to an accident on 14 July 2015, when the pilot of a Robinson R44 helicopter was conducting aerial mustering operations on a property near Alice Springs.
The pilot felt a small vibration, and initially thought it was due to loose tape on the main rotor blade. The pilot looked for a suitable landing site, but the vibration increased significantly.
Carburettor icing can happen at temperatures of up to 38 degrees Celsius – it is less likely at very cold temperatures.
As the helicopter descended, the pilot maneuvered it through a gap between trees, and pushed the cyclic forward to maintain airspeed. The pilot lowered the collective and noticed the engine seemed to go very quiet. The low rotor revolutions per minute warning horn sounded. The pilot made a radio call to advise another pilot operating nearby that the helicopter was going down. The pilot then flared the helicopter to try to cushion the landing impact. The right skid touched down first, and the helicopter rolled onto its right side.
The pilot sustained minor injuries, and the helicopter was substantially damaged. The weather was fine with no visible signs of moisture and the pilot did not turn the carburettor heat on at any stage during the flight.
According to the Carburettor Icing Probability chart, current conditions indicated a high probability of serious carburettor icing at descent power. At the time it was 12 degrees Celsius with relatively high humidity of 40 – 45 per cent.
The icy facts:
Carburettors cause evaporation, which cools the air.
Carburettor icing can happen at temperatures of up to 38 degrees Celsius – it is less likely at very cold temperatures.
Carburettor icing is more likely at partial power settings because of the cooling effect of a partly closed throttle butterfly.
Don’t let lack of sleep affect your fitness to fly.
Pilot fatigue contributed to an incident where an Avro 146 jet received two separate warnings for flying below the minimum altitude, according to an ATSB report.
The incident occurred on 23 June 2015 when the captain and first officer of the Jet Express aircraft were flying from Perth to Granny Smith Airport, north of Kalgoorlie Western Australia. The aircraft had five crew and 67 passengers on board.
While approaching Granny Smith Airport, the captain observed the radio altimeter (RADALT) indicating 500 ft and the electronic ground proximity warning system (EGPWS) called ‘500’, both indicating the aircraft was 500 ft above the ground. Shortly afterwards, the crew received an EGPWS ‘DON’T SINK’ warning. The first officer then observed the RADALT indicating 380 ft and the vertical speed indicator showing about 100 ft per minute descent. The captain immediately applied nose-up pitch and increased the thrust. The aircraft climbed and the captain levelled the aircraft off to remain clear of cloud. The crew then received a second ‘DON’T SINK’ warning. The first officer noted the RADALT indicating 410 ft and the captain immediately initiated a go-around, climbing to 4,000 ft AMSL.
Due to the time spent operating with the aircraft in the approach configuration, and the possibility of holding required in Perth, the captain elected to divert and land at Kalgoorlie.
In the 24 hours before signing on for duty, the captain had about three hours’ sleep and felt irritable, with poor concentration, heavy eyes, and slow thinking processes. The captain believed decision-making had been affected by lack of sleep.
This incident serves as a warning to pilots on how fatigue can affect performance. In fact, less than six hours sleep in the previous 24 hours is associated with degraded operational performance and increased error rates.
Safety message
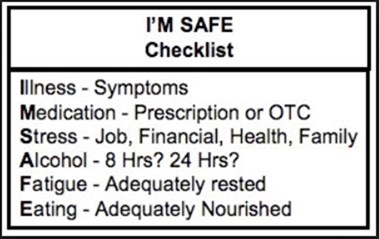
Prior to flight, it is important for pilots to assess their fitness to fly. The following checklist provides a quick reference.
Don’t let lack of sleep affect your fitness to fly.
Less than 6 hours sleep in the previous 24 hours is associated with degraded operational performance and increased error rates.
Fatigue research has demonstrated that humans are quite poor at determining how fatigued they actually are.
The amount of fuel on board should be thought of, not as a quantity, but as a flight time.
Fuel exhaustion happens when an aircraft runs out of usable fuel before the flight is finished.
Fuel exhaustion occurrences are normally either the result of a gross error in the fuelling of an aircraft before flight, or the result of a number of seemingly minor aspects of fuel planning and management during the flight.
Accidents involving fuel exhaustion often happen close to the flight’s destination. If fuel exhaustion occurs when the aircraft is close to landing, it may offer the pilot less time and opportunity to successfully manage the situation.
In April 2010, the pilot of a light aircraft was conducting the fifth flight since refuelling, when the engine lost power while sight-seeing over Hobart, Tasmania. The pilot conducted a forced landing onto the Brooker Highway, resulting in substantial damage to the aircraft.
The pilot reported that he had used a dipstick to assess that there was sufficient fuel for the flight, and that the fuel quantity indicator provided a similar indication of fuel quantity, showing the tank was about half full. Unfortunately, the pilot used an incorrect (but not uncommon) method of using the dipstick that resulted in an over-reading of the fuel onboard. Furthermore, a close inspection of the aircraft’s flight and fuel log would have revealed that the fuel gauge and the dipstick indications showed a fuel usage that was half the expected usage.
What we found
The ATSB investigation AO-2010-025 found that the power loss was due to exhaustion of the aircraft's fuel supply and that a number of factors worked against the pilot, some of which were outside his control.
The amount of fuel on board should be thought of, not as a quantity, but as a flight time.
Cross-checking the dipstick reading against the fuel gauge indication was an effective method for spotting errors, however, a quick mental calculation would have shown a significant discrepancy between the indicated fuel quantity and the expected fuel usage. The discrepancy could have alerted the pilot that something was wrong with the available fuel quantity information.
Safety message
Certain types of flight regularly carry just enough fuel for the flight, with little margin. Flying schools and gliding towing operations may only refuel aircraft after two or three flights, so the last flight before refuelling can have less fuel margin. Charter operations may be flying with minimum fuel required because a flight’s profitability will depend on carrying the maximum payload, which means no unnecessary fuel be carried. Such operations will be more vulnerable to any inaccuracies in the pilot’s knowledge about the amount of fuel on board. However, fuel exhaustion accidents and incidents occur in all types of aviation operations. They are normally related to a lack of awareness of information that is readily available at the pre-flight planning stage. This includes both the amount of fuel on board, and the rate of fuel consumption.
The chance of fuel exhaustion is reduced if the pilot accurately determines the amount of fuel on board prior to starting. This should entail the use of a fuel quantity cross-check using a number of sources, including:
fuel quantity gauges
dipsticks
flowmeters/ totalisers
calculations from previous refuels and fuel usage, (regularly checked for accuracy).
Fuel exhaustion happens when there is no useable fuel remaining to supply the engine(s).
The amount of fuel on board should be thought of, not as a quantity, but as a flight time. For a consistent combination of altitude, power setting and mixture setting, the fuel burn will be constant, but changing winds and deviations due to weather conditions will vary the groundspeed and therefore the range. Your fuel status should be regularly updated, at least every hour, to ensure you maintain an adequate reserve1.
An aircraft that is carrying only just enough flight fuel2 for the planned flight, but which encounters unanticipated headwinds and perhaps has to fly at a lower level is eating into its fuel reserves. Those reserves are there to be used in unforeseen circumstances and many aircraft arrive safely at their destination having used a portion of the allocated reserve fuel. However an aircraft’s fuel supply should not reach a state where, upon arriving at its destination, it can accept no further delay.
1. Reserve fuel refers to the required fuel, in addition to flight fuel, that is not planned for normal use, but remains available for unplanned events where all other useable fuel has been consumed. This fuel is to be used only when there is no other safer alternative.
2. Flight fuel refers to all the fuel that is expected to be used during the planned flight, including holding fuel and fuel for planned diversions.
Conclusion
Fuel exhaustion is more likely to occur on flights when there is little flight fuel margin, that is, landing with just reserve fuel on board. In these circumstances, particular attention to detail in fuel management is warranted. The chance of fuel exhaustion can be reduced by:
using more than one source of information to obtain consistent results about the fuel on board before flight
the use of a consistent procedure that is regularly checked to know the exact rate of fuel consumption
monitoring the flight to ensure that sufficient fuel will remain on board in the event of unplanned delays.
This case study from the Avoidable Accidents Series - Visual flight at night accidents shows that even when undertaken by appropriately qualified pilots, night flight clearly presents an added level of complexity.
In August 2011, the pilot of a Twin Squirrel AS355F2 helicopter and two film crew were travelling to various locations in the Lake Eyre region of South Australia for a television documentary. On the second day, they arrived at an island in the Cooper Creek inlet at about 1715 to meet and interview a tour group.
The pilot and film crew departed the island at about 1900. It was after last light and, while there was no low cloud or rain, it was a dark night. The moon had not risen and there was no visible horizon. Apart from the tour group’s campfire on the island, there was no other source of terrestrial lighting, and there would have been very little ambient illumination from any sources other than stars. Witnesses reported that the helicopter initially climbed vertically while moving rearwards.
This was most likely to maintain a visual reference to the campfire, which was the only available ground light source. The witnesses then observed the helicopter depart in an easterly then north-easterly direction. This was contrary to what they expected as they understood that the crew were returning to their accommodation at Muloorina Station, which was to the south.
Even when undertaken by appropriately qualified pilots, night flight clearly presents an added level of complexity.
The helicopter levelled off at 1,500 ft AMSL and then commenced a turn to the right. As the helicopter had initially travelled in the wrong direction, it is probable that the pilot engaged in programming the helicopter's global positioning system (GPS) for their journey to their accommodation during this turn. Twelve seconds after beginning the turn, the helicopter started descending with the bank angle increasing. Based on the GPS data and flight path estimations, it was calculated that the helicopter impacted terrain at about 1902, about 38 seconds after it started descending. Wreckage examination indicated that the helicopter impacted terrain in a 90° right-side low attitude.
The pilot had been flying for over 30 years as a commercial pilot with over 16,000 hours experience, mostly in helicopters. He also had a night visual flight rules (VFR) rating and had 483 night flying hours in total, but only 3.4 hours in the last 12 months, and 30 hours in the past 4 years. Although he had some instrument flight time, this was more than 30 years before the accident. As such, he probably did not have enough recent night flying experience nor the level of instrument proficiency at the time of the accident needed for the very dark conditions.
The ATSB investigation concluded that the pilot probably became spatially disoriented after initiating the right turn and did not recognise the descent and increasing bank angle in sufficient time to recover.
Lessons learnt
In very dark conditions, visual meteorological conditions (VMC) essentially equates to instrument flight rules (IFR) in terms of available external visual information. Pilots need to reassess their night flying experience, recency and proficiency before every night flight, taking into account the level of instrument flying required based on the level of darkness.
Any pilot can become spatially disoriented given the right conditions. Distractions and high workload can inadvertently remove attention away from monitoring instruments, reducing the chance of recognising spatial disorientation.
The ATSB advises all operators and pilots considering night flights under the VFR to systematically assess the potential for the flight to encounter dark night conditions by reviewing weather conditions, celestial illumination and available terrain lighting. If there is a likelihood of dark night conditions, the flight should be conducted as an instrument flight rules (IFR) operation, or conducted by a pilot who has an IFR-equivalent level of instrument flying proficiency and in an aircraft that is equipped to a standard similar to that required under the IFR.
Conclusion
Data from accidents associated with the risks from night visual flight indicate that they can affect pilots at all stages of experience or qualification, in any type of aircraft. Pilots do not become immune from these risks as experience increases. The harsh outcomes of night accidents can be seen in the photos throughout this booklet. Three in four accidents involving visual flight at night have fatal outcomes.
The risks associated with night visual flying cannot be avoided—they must be understood, identified and managed. Control problems can be identified by cross-referencing information from flight instruments. They can be managed by focussing on aircraft control and using the most reliable information source. The risks from controlled flight into terrain can be managed by calculating LSALTs (lowest safe altitude), knowing terrain elevation during the cruise, and knowing where hills and obstacles are in the circuit area during take-off and landing. The knowledge can be obtained by thorough pre-flight preparation, by accurate horizontal navigation to know where you are, and accurate vertical navigation to know your distance from obstacles below. Everything is more difficult to see at night. Terrain and obstacles are often not illuminated, and it is more difficult to detect cloud. When it is time to fly low enough to land, a detailed plan of how to avoid all obstacles along the expected flightpath is necessary to maintain safety.
Visual night flying is sufficiently different from both day visual flight and (except in very dark conditions) instrument flight that it needs to be treated as a separate skill in its own right. It requires a disciplined integration of two very different skill sets of instrument flight and degraded visual flight to develop sufficient situational awareness to enable safe flight. To maintain these skills, a pilot needs to have enough recent experience and practice. When flying over land or oceans without light sources, on dark nights with no visible moon, visual flight at night is essentially the same as instrument flight.
Before every night flight, systematically assess the potential for the flight to encounter dark night conditions by considering weather conditions, celestial illumination and available terrestrial lighting. Only fly in environments that do not exceed your capabilities. In very dark conditions, consider following instrument procedures if you are rated or avoid areas with limited terrestrial lighting if you are not.
In night visual flight, there is more chance of any pilot becoming influenced by illusions. Have a coping strategy in place, and be prepared to revert to instrument flight to recover from any spatial disorientation.