Coordination is key to airside safety

Safety Advisory Notice

Effective coordination and communication between airside crews could help prevent or detect mistakes that led to a collision between an Airbus A330 and aerobridge during boarding.

What happened

On 31 March 2016, an Airbus A330 was being boarded at Melbourne Airport, Victoria. Seeing that the parking brake was on, a maintenance engineer removed the main chocks early. The crews removed the nose gear chocks to dock the towbarless tractor without checking the main gear chocks. The captain, unaware that no chocks were in place, released the park brake and the aircraft rolled back, striking the aerobridge. There were no injuries and the aircraft door and aerobridge were damaged.

Why did it happen

The ATSB found that the ground and flight crew procedures were not harmonised, reducing cohesion between the crews. In the absence of clear guidance or instruction on coordinating activities during pushback, and based on incorrect assumptions, key steps involving the chocks and parking brake were performed out of sequence and without being communicated between tractor, engineering and flight crews.

Damaged forward-left door

Figure 2: The aircraft’s forward fuselage showing the dislocated forward-left door. The slight indentation in the fuselage skin forward of the door is not visible. The aerobridge is shown retracted from its position when struck by the aircraft

Source: Melbourne Airport, modified by the ATSB

Safety advisory notice

Effective coordination and communication between airside crews can prevent or detect mistakes that could otherwise lead to damage or injury. The ATSB advises organisations that work airside to ensure that ground and flight crew activities are harmonised, and to foster active communication and coordination between working crews.

Communicate and coordinate airside activities

An aircraft is attended at a terminal bay by people carrying out a wide range of concurrent tasks. Typically, they and their respective organisations work alongside many others, each operating with different processes and to varying contractual arrangements. Defining a set of processes that can apply across such varied situations and aligning them well with the other activities can be difficult. In practice, mechanical malfunctions and honest mistakes can rarely be completely eliminated. An effective procedure will include steps to ensure that activities are appropriately aligned with other procedures. One way to achieve this is to pause and check if the situation is as it should be, and to inform others of activities that could affect them.

Read more about this ATSB investigation: atsb.gov.au/investigations/ao-2016-028


Publication details

Investigation number AO-2016-028-SAN-006
Publication type Safety Advisory Notice
Publication mode Aviation
Publication date 13/09/2016

Why it pays to go-around

A hard landing of a Maule MT-7-235 aircraft at Greenfields airstrip near Noosa in Queensland on 16 May 2016 highlights why it’s important for pilots to conduct a go-around when in doubt.

ao2016049_news.jpg

The requirement for three take-offs and three landings in the last 90 days is a regulatory requirement for pilot currency, but this does not guarantee pilot proficiency. Pilots need to be ‘go-around prepared’ because the execution of a go-around is an infrequent manoeuvre.

The pilot had flown about five flights, totalling about 20 hours in the previous 12 months and the pilot’s last flight was about four-to-five weeks prior to the accident flight.

When flying infrequently, proficiency in take-offs and landings can be improved by dedicating a portion of the flight to practicing circuits, including go-arounds. The United States Federal Aviation Administration describes this as ‘imbuing the quantity of flying, however limited, with quality.’

The Maule pilot conducted a private flight from Greenfields with two passengers on board. After a trip that included a re-fuel at Gympie, the flight headed north towards Maryborough before returning to Greenfields along a coastal route.

On final approach to Greenfields, the pilot noticed they were getting low. At about 500 ft, they increased the power to regain their approach path. The pilot subsequently assessed that the aircraft was too high and lowered the nose to re-intercept the approach path.

The pilot flared the aircraft for landing, the aircraft landed heavily and bounced into the air. As the aircraft landed again, the nose wheel touched down first (before the main landing gear) with sufficient force that the nose wheel strut fractured.

The nose landing gear and propeller then dug into the ground and the aircraft rotated over its nose and slid a short distance inverted before coming to rest. The pilot and one passenger were uninjured, another passenger sustained minor injuries, and the aircraft sustained substantial damage.

The pilot had not operated the Maule aircraft with more than one passenger on board prior to the accident flight and felt that the higher all-up-weight of the aircraft with an extra passenger on board may have contributed to a higher sink rate on final approach.

The pilot later formed a view that a go-around, rather than continuing with the landing manoeuvre, would have been a better option.

Take-off and landing phases of flight are critical, since the aircraft is operating closer to the stall speed and with less height to recover from a control problem, relative to cruise flight.

A go-around could have prevented an unstable approach and initial bounce from escalating to an accident.

Read the final report: Hard landing involving Maule MT-7, VH-DRS, near Noosa, Queensland, on 16 May 2016

Runway incursion results in airport safety improvements

Enhanced safety actions will help reduce risks for aircraft and ambulance operators at Blackall Airport in Queensland.

blackall-airport-news.jpg

This follows a runway incursion involving an aeromedical Hawker Beechcraft B200 aircraft and an ambulance on the night of 28 February 2016.

At about 2.30 am the plane was descending to Blackall Airport with a pilot, a doctor and a nurse on board.

Earlier, at about 2.20 am, an ambulance driver was dispatched to Blackall Airport by the ambulance coordination centre to meet the aircraft for patient transportation. The ambulance driver was the only occupant of the vehicle.

A series of events involving missed communication and sighting between the ambulance and the aircraft resulted in the Beechcraft B200 initiating a missed approach.

The pilot climbed and entered a hold pattern about 5,000ft above the airport before descending and landing without incident.

As a result of this occurrence, the aircraft and ambulance operators have advised the Australian Transport Safety Bureau (ATSB) of a range of safety actions to be implemented.

For the aircraft operator, runway strip inspections will continue for night operations at all aerodromes with known or suspected animal hazards and where appropriate ground personnel can safely conduct inspections.

Formal procedures will be developed in conjunction with the ambulance operator detailing safety procedures for those rural/regional stations where a request for a runway inspection is likely.

Appropriate procedures will be developed for requesting airstrip inspections for incorporation in the airstrip data manual.

And there will be closer safety liaison between the respective ambulance and operator safety departments.

The ambulance operator has advised the ATSB that staff working at Blackall Airport will attend the airport operator induction program.

Consultative arrangements with occur with key stakeholders and there will be a review of local UHF/VHF radio communications procedures between the operation centre, aircraft operator, airport operator, and ambulance attending the airport.

In addition, there will be a review of induction programs for staff in consultation with the aircraft operator and the airport. All new and existing staff will participate in a revised induction program. Induction workbooks will be reviewed and all new and existing staff will be provided with a copy of the workbook.

A review of the Blackall standard operating procedures will be conducted to ensure that procedures cover all aviation safety requirements.

The International Civil Aviation Organization (ICAO) has identified runway safety as one of its priorities and has been working with countries and aviation organisations globally to reduce runway safety accidents. ICAO has a runway safety website and has published a Manual on the prevention of runway incursions (Doc 9870 AN/463), available on the website.

Additional information on runway safety is available from Airservices Australia, including The airside drivers guide to runway safety.

Read the final report: Runway incursion involving Hawker Beechcraft Corporation B200, VH-FDG, and vehicle, Blackall Airport, Queensland, on 28 February 2016

Smoking device

An effective response to an emergency situation ensured the safe arrival of Qantas Airbus A380 flight QF7 from Sydney to Dallas, Texas, on 15 May this year.

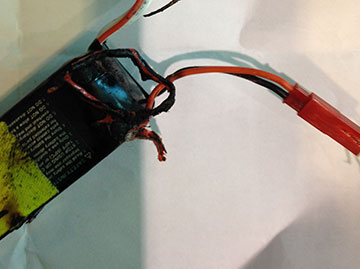
ped-lithium-battery.jpg

About two hours prior to arrival at Dallas-Fort Worth, United States, a passenger alerted cabin crew to smoke in the cabin. Cabin crew initiated the basic fire drill procedure and the customer service manager (CSM) made an emergency call on the aircraft interphone to alert all crew to the presence of smoke.

Cabin crew located the source of the smoke and removed seat cushions and covers while the CSM turned off power to the centre column of the seats.

On further investigation, the crew found a crushed personal electronic device (PED) wedged tightly in the seat mechanism. The PED contained a lithium battery.

A rapid and coordinated response by the crew ensured the situation was effectively managed and the safe landing of the aircraft.

The incident highlights the hazards of transporting lithium-ion battery powered PEDs on aircraft. More than a billion lithium batteries are believed to be transported by air every year, with potentially hundreds carried on single sectors on large aircraft.

The ATSB has received 17 notifications of similar incidents of lithium battery thermal events in aircraft over the past six years.

Cabin crew and passenger education remains a key component to managing these events. The Civil Aviation Safety Authority web page Travelling safely with batteries and pamphlet Is your luggage safe? provides information on the safe carriage of lithium-ion batteries and lithium-ion powered devices aboard aircraft.

Read the final report: Smoke event involving Airbus A380, VH-OQD, about 1,500 km west-south-west of Dallas-Fort Worth Airport, United States, on 16 May 2016

Smoke and fumes

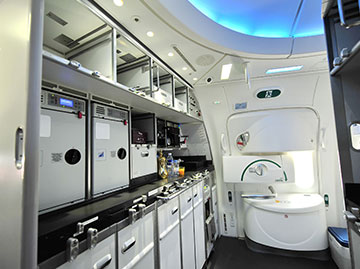
Correct management of an abnormal situation and effective crew coordination ensured the safe return of a United Airlines Boeing 787 to Sydney on 17 April this year.

boeing787galley_news.jpg

An Australian Safety Transport Bureau (ATSB) investigation found that all emergency procedures were carried out efficiently and effectively. The captain involved all relevant crewmembers and the ground-based technical operations maintenance controller (TOMC) in making a decision to return the aircraft to Sydney.

The situation occurred when a faulty oven resulted in smoke and fumes setting off a fire alarm on the San Francisco-bound flight UAL870, comprising 238 passengers, 11 cabin crew and four flight crew.

During departure, cabin crew switched on the aft galley ovens in preparation for meal services. After the two ovens were switched on, there was a short burst of smoke, with one of the ovens displaying a “FAILURE” message.

Several cabin crew detected a strong chemical odour and an electrical smell, as well as a blue haze. Other crew described it as an ozone smell. The oven interactive screen displayed a ‘Critical Error- Broken Fuse’ message.

The crew immediately pulled all relevant circuit breakers, and switched off all electrical sources to the aft galley. The inflight service manager (ISM) advised the captain. The ISM and a relief pilot from the cockpit arrived at the aft galley with fire extinguishers. By this stage, the smoke had dissipated, but the odour persisted. As it could not be confidently ascertained that the ovens were the sole source of the problem, the captain contacted the TOMC by satellite phone.

The discussion with the TOMC involved all flight crew and the ISM. It was agreed that the safest option was to return the aircraft to Sydney. The captain advised ATC by a PAN call. ATC initiated an INCERFA phase. About 110 km east of Port Macquarie, NSW, the crew commenced a return to Sydney. As the aircraft was well in excess of its allowed landing weight, fuel was dumped during the descent.

The aircraft landed without incident in Sydney at 1258 Eastern Standard Time (EST) with emergency services attending.

A post-engineering inspection quarantined the suspect oven, and after an inspection, a fuse was replaced. After appropriate testing, the aircraft was released back to service.

Boeing and the oven manufacturer investigated the cause of the ‘Critical Error’ fault displayed on the oven screen. The manufacturer individually tested all oven components. They reported that all individual components worked correctly, however, an additional measurement of the oven motor current detected that the motor did not run smoothly. The motor temperature was also above normal, most likely from insufficient airflow. This known fault had been rectified with a new oven software release.

Boeing reported that the oven manufacturer was working with United Airlines to update the software in all relevant ovens in their fleet. The exact cause of the odour could not be determined.

Read the final report: Smoke and fumes event involving Boeing 787, N36962, 110 km east of Port Macquarie, New South Wales, on 17 April 2016

No risk assessment done before worker struck by train

An accident where a rail worker was struck by a passenger train near Laverton station in Victoria shows why it’s essential workers follow safeworking rules and procedures when working on or near railway tracks.

trackworkerstruck_news.jpg

A report by the Australian Transport Safety Bureau (ATSB) found that on the morning of 2 October, 2015, a track was accessed by a workgroup without an assessment of risks and without the establishment of appropriate risk controls.

This meant that not all in the group had a clear understanding of train movements that morning, nor was there a defined position of safety known to all the workers.

The ATSB found that the train was given the all clear to proceed prior to the supervisor moving to a position of safety, clear of all tracks. There were several breaches of safeworking procedures that, while not directly contributing to this accident, increased the risks associated with the workgroup’s activities.

On that Friday morning, track workers were assembling track-side in Laverton, Victoria. They planned to undertake dogspike removal works in preparation for re-sleepering of a section of track on the Altona Loop Line.

At around 0910, the supervisor for the works began marking the track to identify those dogspikes to be removed. He was working in a track crossover about 400m on the Melbourne side of Laverton Railway Station. A lookout had been stationed for his protection.

At about 0916, a Metro Trains Melbourne suburban commuter train arrived at Laverton station, bound for Flinders Street Station in central Melbourne. After its scheduled stop, the train departed Laverton and approached the worksite. The lookout observed the train, warned workers of its approach and signalled to the driver that the track was clear.

However, as the train took the crossover, the supervisor was foul of the track, and was struck by the train travelling at about 59 km/h. The supervisor suffered serious injuries.

The supervisor was foul of the track when the train reached his location. It is probable that he expected the train to continue along an adjacent track, and not take the crossover towards his location.

Since the incident, Metro Trains Melbourne has increased the frequency of audits of infrastructure worker compliance with safeworking procedures.

The key safety message is that working in rail corridors carries significant risks that should be mitigated by adhering to established safeworking procedures.

Read the final report: Track worker struck by passenger train, near Laverton station, Victoria, on 2 October 2015

Additional information about safe work on rail.

Lithium battery warning

The Australian Safety Transport Bureau (ATSB) is urging air passengers to strictly follow government safety advice when travelling with lithium batteries.

battery_news.jpg

This follows an 11 August 2016 incident on a QantasLink Dash8 aircraft prior to departure at Sydney airport.

The flight was fully boarded and loaded when smoke was observed coming from a passenger’s hand luggage while it was in the overhead locker.

With fumes in the cabin, air crew initiated disembarkation procedures and the passenger was escorted to a safe area to isolate the hazard. The remaining passengers, including a wheelchair passenger, were escorted to an evacuation area.

Mobile and other electronic devices such as phones, laptops, watches and cameras containing low power lithium or lithium-ion batteries should be included in carry-on baggage only—not checked-in baggage.

The passenger’s luggage was made safe, the flight was cancelled, and passengers were moved to next service. Fortunately, no one was seriously injured but some passengers suffered side-effects from the smoke.

It was later found that the lithium batteries the passenger was carrying had ignited on board the aircraft. The operator reported that the batteries were not packaged properly (either in their original packaging or packed individually to insulate the terminals) to protect them from short circuiting.

ATSB Chief Commissioner Greg Hood said government authorities worked closely with airlines and the aviation industry to minimise the risk of aviation incidents.

“With the use of mobile devices at an all-time high, the Civil Aviation Safety Authority (CASA) has placed a greater focus on the carriage of personal electronic devices when flying,” Mr Hood said.

“Mobile and other electronic devices such as phones, laptops, watches and cameras containing low power lithium or lithium-ion batteries should be included in carry-on baggage only—not checked-in baggage.

“All spare batteries for these devices should also be placed in carry-on luggage and packaged individually to insulate the terminals to protect them from short-circuiting.

“Incidents are more likely to occur when spare batteries, such as for digital cameras, are not packaged to insulate the terminals, as was the case in this incident.

“The Australian Government has in place regulations designed to ensure the safety of passengers, but it is also everyone's responsibility to declare dangerous items and to ensure electronic devices are not only in good order but packaged according to CASA’s requirements.”

For more information visit CASA’s Advice for air travellers(Opens in a new tab/window).

Birdstrike!

An incident where the pilot of a Glasair Sportsman GS-2 was temporarily blinded after a large eagle broke through the windscreen, highlights the serious hazards of aviation wildlife strikes.

damaged-glasair-sportsman-aircraft.jpg

On 24 December 2015, the pilot of a Glasair Sportsman GS-2 was conducting a private flight from Southport, Queensland, to Moruya, New South Wales (NSW), with a refuel stop at Mudgee, also in NSW. The pilot was the only person on board.

While cruising at 5,500 ft above mean sea level near Bathurst, NSW, the aircraft collided with a large bird, believed to be a wedge-tailed eagle. The bird broke though the windscreen on the left side of the aircraft and struck the pilot. The collision left the pilot with serious facial injuries and they were temporarily unable to see. The pilot was wearing a headset and spectacles, which were both dislodged and damaged during the collision. Following the birdstrike, the aircraft entered a rapid descent, but the pilot recovered sufficiently to regain control. Despite the broken windscreen and their injuries, the pilot was able to divert to Bathurst Airport and land successfully.

During their ordeal, the pilot had been able to locate the microphone of the headset and transmit a MAYDAY call. But damage to the headset meant they were unable to hear any incoming transmissions. Although air traffic control (ATC) received the MAYDAY call, they did not know the callsign or specific location of the aircraft involved, or the intentions of the pilot. About 30 minutes after the MAYDAY call, the Safety Officer at Bathurst airport contacted ATC to advise them that an aircraft with a broken windscreen (the result of a birdstrike) had landed at Bathurst.

ATSB research report (AR-2104-075) titled Australian aviation wildlife strike statistics provides some insights into the nature and characteristics of birdstrikes. The August 2010 edition of the Flight Safety Foundation magazine (AeroSafety World) includes an article titled Bird Strike Mitigation Beyond the Airport(Opens in a new tab/window), which provides some interesting comments regarding bird behaviour and the possible effects of a birdstrike on general aviation aircraft.

This incident highlights the serious hazard to aviation presented by birds, not only near aerodromes. A birdstrike can cause substantial damage which has the potential to significantly adversely affect the performance and handling qualities of an aircraft. When declaring an emergency, pilots are encouraged to relay as much relevant information as reasonably possible (acknowledging that the circumstances surrounding this incident made effective communication very difficult). Positional information and information with respect to the intentions of the pilot may be critical to an effective response by emergency services.

Read the final report: Birdstrike involving Glasair Sportsman GS-2, N666GM, near Bathurst, New South Wales, on 24 December 2015

Fatal truck–train collision prompts safety action

The ATSB is urging road and rail authorities to consider safer road design at railway crossings, after a tragic collision between a road-train truck and grain train.

truck_narromine.jpg

On 23 September 2015, an eastbound road-train truck, hauling grain, collided into the side of Pacific National grain train 8834N, (travelling on the main line between Narromine and Peak Hill) at the Tullamore – Narromine Road railway crossing, about 4 km southwest of Narromine, in New South Wales. The railway crossing was controlled by flashing lights, an audible warning device (bell); passive warning signs installed on the road approaches and road surface markings.

The collision and a post-impact fire destroyed the prime mover and one of the two trailers; the truck driver was fatally injured. The crew of the train were physically unhurt. As a result of the impact two wagons, were damaged, one of which derailed. Some of the railway crossing infrastructure (flashing lights) was destroyed and required replacement.

The ATSB found that the driver of the road-train truck was probably travelling too fast for the prevailing conditions, and entered the Tullamore – Narromine Road railway crossing while it was active, and the flashing lights were operating. It was concluded that the truck driver’s attention was probably focussed on negotiating the sweeping right-hand curve that preceded the crossing, at a critical time when he needed to check for the activation of the crossing. It is likely that when the driver perceived that the flashing lights were operating, he was too close to the crossing to stop, and collided with the train.

The ATSB identified a number of areas of potential improvement related to road design (signage and standards associated with railway crossing traffic control) especially with respect to curved approaches, before railway crossings.

Furney Flour Mills, the Narromine Shire Council, and Standards Australia have implemented a range of initiatives to reduce the risk of a similar occurrence in the future, including:

  • enhanced employee training and medical assessment initiatives
  • provision of additional (road) approach passive warning signs, (W7-4) plus a review of road alignment and railway crossing road approach speeds
  • a review of AS 1742.7-2016, with respect to railway crossing approaches, in particular curved approaches, and the location of signage.

Safety message

Although the road rules (NSW - Road Rules 2014) make motorists primarily responsible for avoiding a collision with a train at railway crossings, prudent road design and/or advance warning of a train’s presence at railway crossings should be considered as a strategy to lower the risk of road and rail vehicle collisions.

Road and rail authorities should consider added measures to enhance the situational awareness of motorists approaching railway crossings, especially at locations with restricted sighting due to curved approach roads.

It is imperative that road vehicle drivers always approach railway crossings with extreme care. The level of care and attention required increases as road vehicle gross mass increases.

Read the final report: Collision involving road-train truck and train 8834N, near Narromine, New South Wales, on 23 September 2015

Fumes in the cabin

The crew of this Tiger Airways A320 followed emergency procedures effectively to handle a potentially serious situation that affected three cabin crew members.

tigera320_news.jpg

On 1 March 2016, a Tiger Airways Airbus A320 aircraft departed Brisbane, Queensland, on a scheduled passenger service to Melbourne, Victoria. On board were the captain, the first officer, four cabin crew members, and 63 passengers.

At about 0900 when the aircraft was above Parkes, New South Wales, the cabin crew detected a strong odour in the rear of the cabin, and notified the captain. The cabin crew were unsure what the smell was, but they later described it as being similar to an extinguished cigarette.

At 0933, as the aircraft was about 211 km north of Melbourne, the cabin crew manager advised that three cabin crew members were feeling unwell, and that one had vomited.

The flight crew contacted air traffic control, declared a PAN, and requested direct tracking to Melbourne. The captain advised the passengers that fire vehicles and ambulance would be present for their arrival at Melbourne Airport. 

After landing, the aircraft taxied to the bay, followed by the airport rescue and firefighting service. After shutting the engines down, the captain advised the fire commander that other than sick members of the cabin crew, everything was normal. The fire crew did not find any source of fumes or fire, nor did a subsequent engineering inspection reveal the source.

This incident demonstrates effective crew resource management techniques to deal with an abnormal and evolving situation.

Read the final report: Fumes event involving Airbus A320, VH-VNO, 211 km north of Melbourne Airport, Victoria, on 1 March 2016