

Cessna 150 stalled in strong and gusty winds

A Cessna 150 stalled shortly after taking off in strong and gusty wind conditions at Bacchus Marsh, north‑west of Melbourne, and was too low to recover before colliding with terrain, an ATSB investigation has concluded.
On the morning of 22 October 2024, a solo pilot intended to fly the Cessna 150L single piston‑engine aircraft from Bacchus Marsh Aerodrome, to Lethbridge, Victoria.
After lining up on runway 27 in strong and gusting winds, the pilot began and then rejected a take‑off roll.
The pilot broadcast the rejected take‑off on the aerodrome’s common traffic advisory frequency, but did not provide any further information as to why the take‑off was rejected.
The pilot then returned to the end of runway 27 and began a second take‑off attempt.
After leaving the runway the aircraft climbed 150 ft, before pitching steeply nose‑up.
Witnesses then observed the nose, then the left wing, drop, before the aircraft entered a vertical descent and collided with terrain in a paddock beside the airfield.
The aircraft was destroyed, and the pilot was fatally injured.
An ATSB transport safety investigation did not identify any issues with the aircraft which could have contributed to the accident, and a post‑mortem examination did not find any evidence of pilot incapacitation or substances which could have affected their capacity to perform the flight.
The investigation concluded the aircraft was probably too slow on take‑off in the strong and gusty wind conditions, and that inputs made to counteract the crosswind increased the angle of attack of the left wing.
“These factors, combined with the wind conditions, increased the risk of a quick and unrecoverable stall,” ATSB Chief Commissioner Angus Mitchell said.
“The stall occurred too close to the ground for the aircraft to be recovered from.”
While an aerodynamic stall can occur at any airspeed, altitude or engine power setting, Mr Mitchell said this accident demonstrated why they are most hazardous during take‑off and landing, when the aircraft is close to the ground.
“When gusting conditions are present, pilots should consider waiting for more benign conditions,” he said.
“Guidance advises pilots to conduct their own testing in progressively higher winds to determine both their own capability and that of the aircraft.”
“If pilots judge weather to be suitable, they should consider climbing out at a higher airspeed to provide a buffer above their aircraft’s stall speed for detection and correction of an impending stall.”
Read the final report: Loss of control and collision with terrain involving Cessna 150L, VH-EYU, Bacchus Marsh aircraft landing area, Victoria, on 22 October 2024
Propeller strike of a taxiway edge light involving Beechcraft King Air B200C, VH-RFD, Hobart Airport, Tasmania, on 1 July 2025
Final report
Report release date: 05/12/2025
Investigation summary
What happened
At 1807 local time on the evening of 1 July 2025, a Royal Flying Doctor Service Beechcraft King Air B200, registered VH-RFD, with 2 pilots and a paramedic on board, taxied at Hobart Airport, Tasmania, for a night flight to Launceston. As the aircraft taxied to conduct a 180° turn using the runway 30 turnaround pad, it struck a taxi light with the right propeller. The aircraft incurred damage to the propeller and a turnaround pad edge taxi light was also damaged.
After recognising the strike had occurred, the pilots reported it to air traffic control, returned to the parking apron and grounded the aircraft.
What the ATSB found
The ATSB found that the pilot flying subconsciously mistook the blue taxiway edge lights and double yellow line on the edge of the turning pad as taxi centreline guidance. This resulted in the pilot deviating from the marked taxiway centreline towards the runway edge light, resulting in the propeller strike.
The ATSB also found that the supervising pilot’s intervention did not occur in time to prompt the pilot flying to adjust the taxi route before impacting the edge light.
Safety message
All pilots are susceptible to human error. This incident highlights that pilots need to be vigilant and maintain an awareness of their location.
The airport environment contains numerous visual aids, markings, signals and signs. Pilots must remain situationally aware of their location, traffic and intended ground tracks to avoid obstacles. When the taxiway is suitable for the aircraft type, it is usually safest to follow the yellow line when taxiing at night, in reduced visibility or at an unfamiliar aerodrome.
Additionally, effective monitoring in a multi-crew environment is also paramount to aircraft safety. Bringing deviations to the early attention of the pilot flying promptly ensures the aircraft remains on a desirable track.
The investigation
| The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities. |
The occurrence
At 1807 local time on 1 July 2025, a Beechcraft King Air B200, registered VH-RFD, operated by the Royal Flying Doctor Service (RFDS) with 2 pilots and a paramedic on board, commenced taxiing at Hobart Airport, Tasmania. The intended destination for this flight was Launceston Airport. It was dark, with little to no moonlight, and good visibility.
The pilot flying (PF) was operating under the guidance of a supervisory pilot (SP), prior to their final line check,[1] which was scheduled in 2 shifts time. The PF occupied the left‑hand side control seat in the cockpit. The SP, who was also designated pilot in command (PIC),[2] occupied the right-hand control seat.
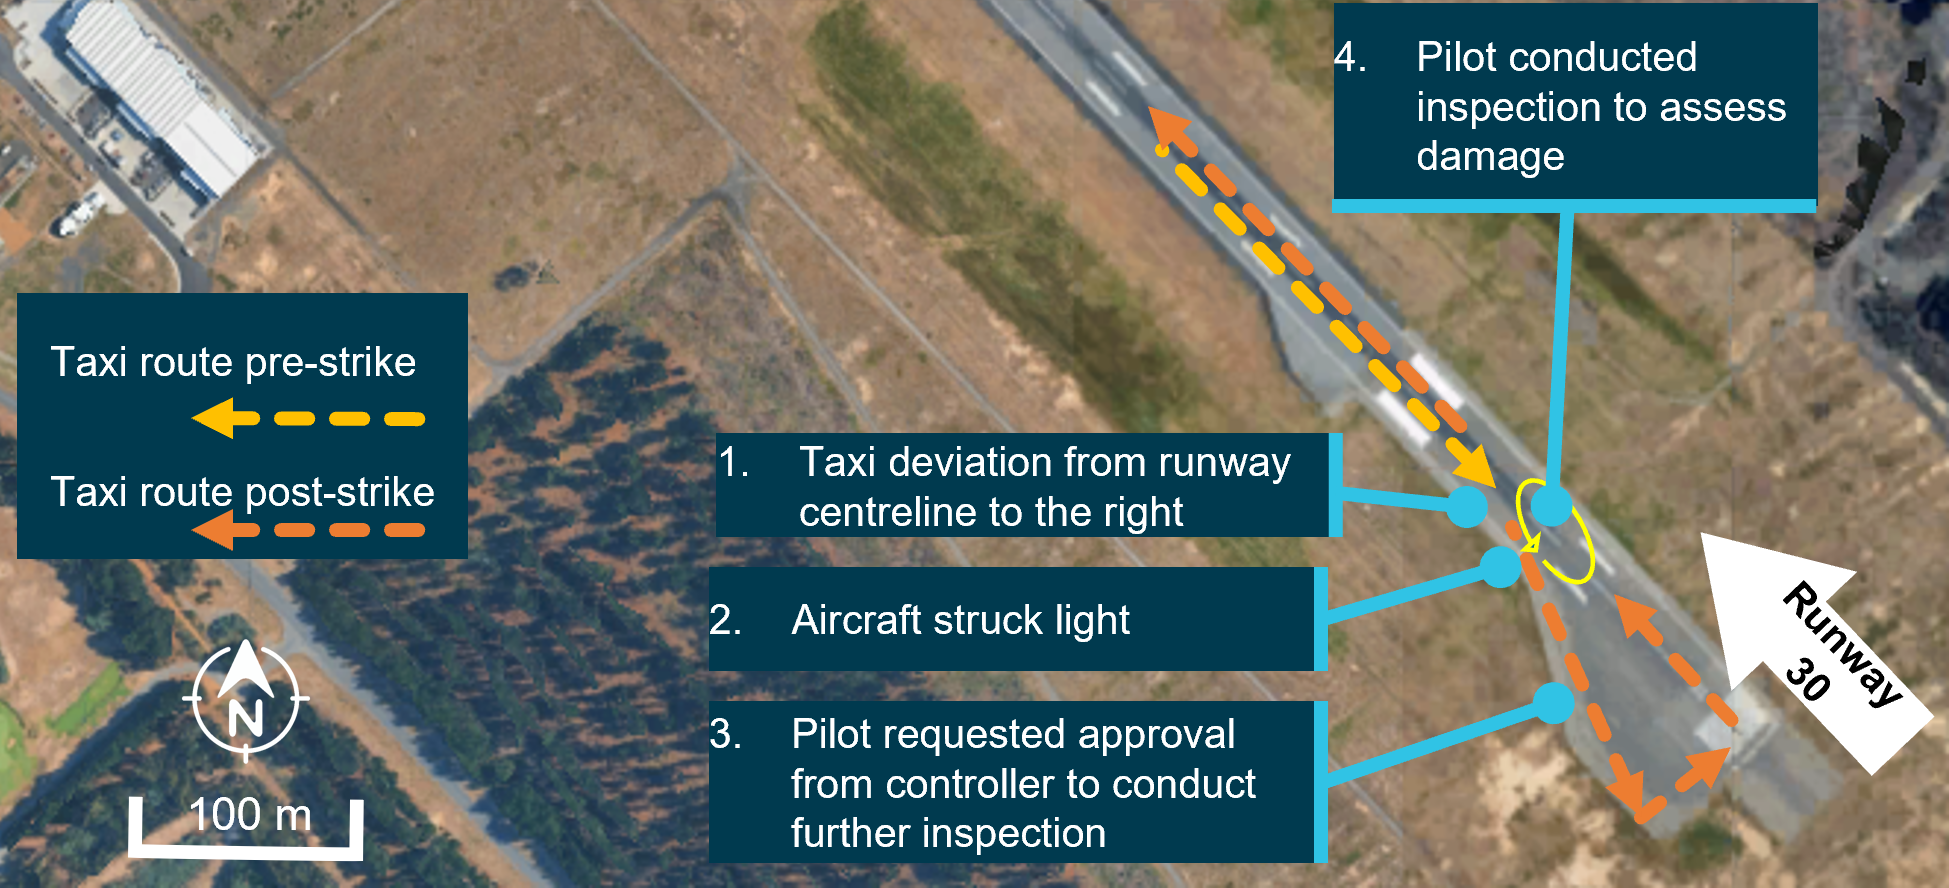
At 1810, the aircraft entered runway 30 to backtrack[3] so that the full runway length could be used for take-off (Figure 1).
Figure 1: Taxi route
Source: Google Earth, annotated by the ATSB
The pilots reported that a common technique for taxiing and turning the King Air B200 is to make a wide arc turn to reduce stress on undercarriage components.
During taxi, the PF steered the aircraft away from the centreline taxiway ground markings, toward the right runway edge, approximately 100 m prior to the runway threshold (Figure 1, label 1). This manoeuvre was to position the aircraft for a 180° turn via the runway turnaround pad (a wide, paved area that allows room for aircraft to reverse taxi direction).
The pilot reported that they subconsciously mistook the blue taxiway edge lights and double yellow line on the edge of the turning pad as taxi centreline guidance. This subsequently resulted in positioning the aircraft to the far right of the turning pad, aligning the aircraft with the double yellow line runway edge light rather than the single yellow line. A reconstructed visual perspective, replicating what the pilot may have seen is shown in Figure 2.
Figure 2: Reconstructed pilot view, approaching and entering the turnaround pad
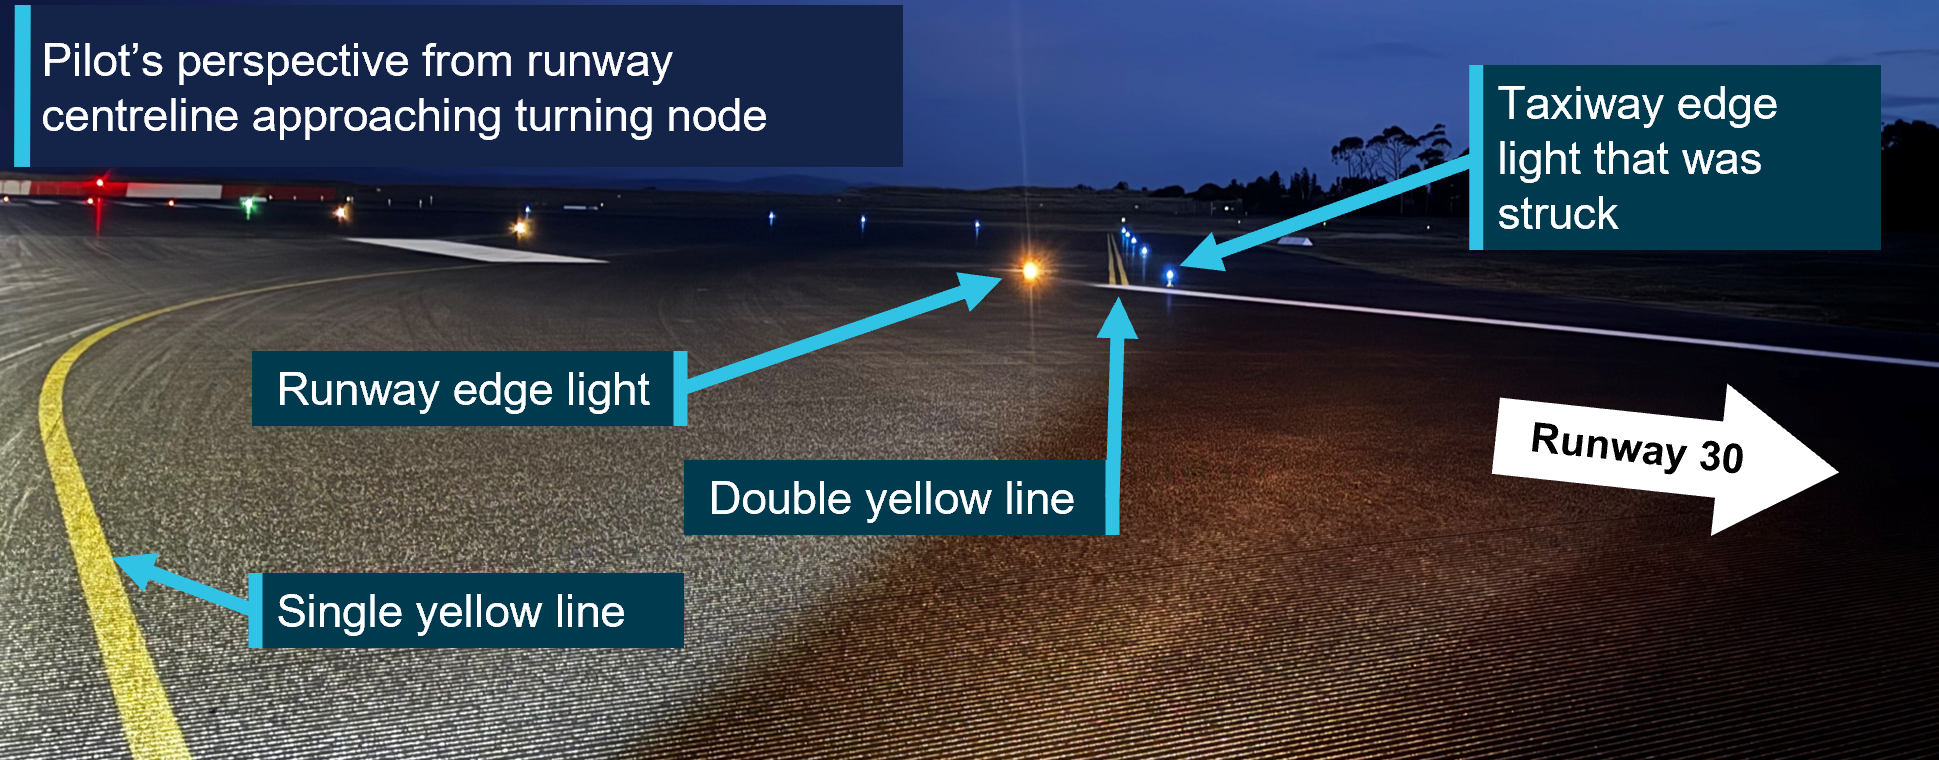
These images were taken post-occurrence. The height of the camera was lower than the pilot’s sightline during the incident. Source: Hobart Airport, annotated by the ATSB
The wide turn taken by the PF was consistent with what was expected by the SP. As the aircraft approached the right side of the turnaround pad, the SP recalled that they were waiting for the PF to turn the aircraft as it came into the proximity of a taxiway edge light. Once the SP identified that the aircraft was close to the edge light, the SP advised the PF. However, before the PF could steer away from the light, the right propeller struck it (Figure 1, label 2).
Suspecting the aircraft had struck the light, the PF requested from air traffic control (ATC) clearance to conduct a further ground inspection to assess for damage (Figure 1, label 3 and label 4).
The pilot then confirmed with ATC that the aircraft had struck the light (Figure 3) and advised that they would need to return to the apron.
Figure 3: Blue pad edge light damage
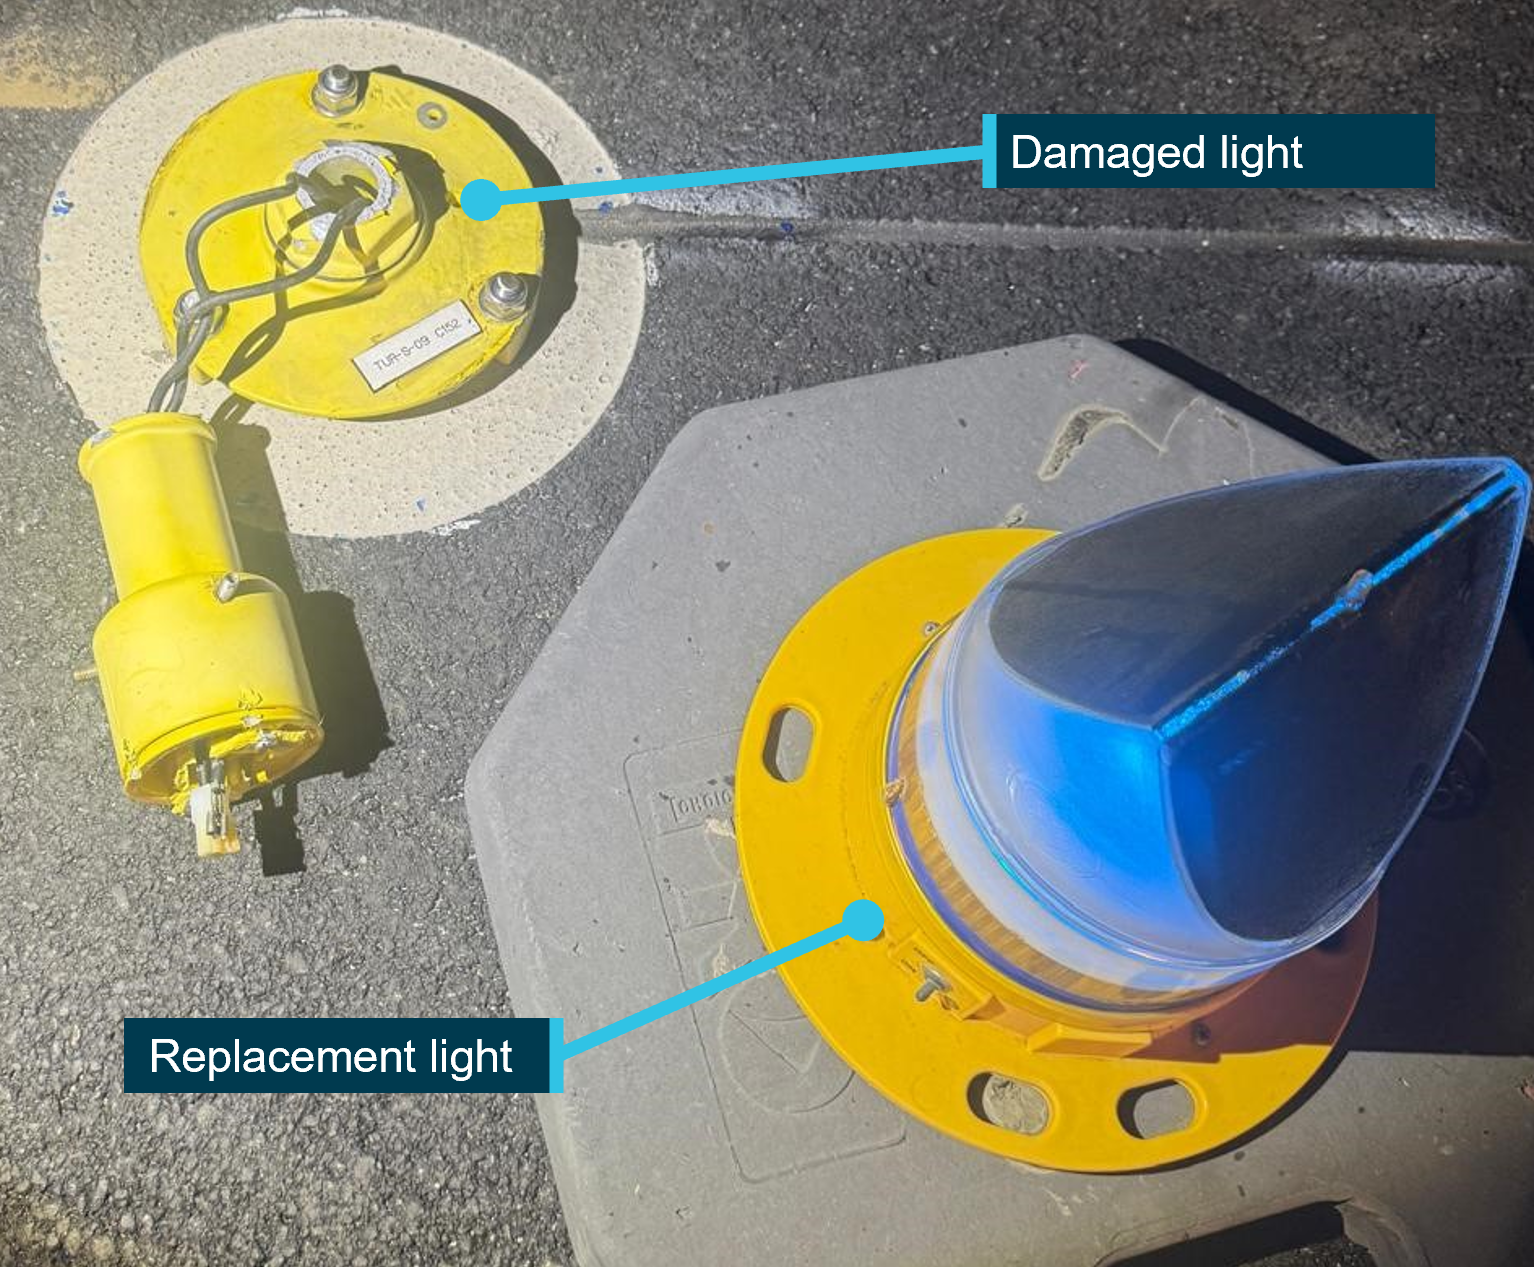
Source: Hobart Airport, annotated by the ATSB
After shutting down the aircraft, the pilots inspected the aircraft and identified damage to the right-hand side propeller (Figure 4).
Figure 4: Propeller damage

Source: RFDS
Context
Pilot information
Pilot flying
The PF held a commercial pilot (aeroplane) license and a valid class 1 aviation medical certificate. They reported a total flying time of about 4,920 hours with about 76 of those being on the King Air B200, having joined the RFDS in April 2025. They reported completing 5 previous flights to Hobart prior to the occurrence, as part of their line training under supervision. All except one of those flights involved the runway 30 threshold being displaced, and they did not utilise the turnaround pad.
Prior to joining the RFDS, the pilot had held training and examining approvals as well as key management positions at another operator.
Prior to the incident, the SP had assessed the PF as capable and their flying standard was reflective of that of a candidate approaching their final check.
Supervisory pilot
The SP held an air transport pilot (aeroplane) license and a valid class 1 medical. They reported a total flying time of 11,848 hours with 4,876 of these hours being on the King Air B200. They also held a management pilot role.[4]
Aircraft information
The Beechcraft King Air B200 is a pressurised, low-wing, twin turbine-engine aircraft with retractable landing gear. The aircraft had a certified maximum take-off weight of 5,667 kg and could be flown by a single pilot. The aircraft, serial number BL-171, was manufactured in the United States in 2014 and subsequently registered in Australia on 14 August 2014. The Royal Flying Doctor Service of Australia (South Eastern Section) had been the registered operator of the aircraft since August 2014.
Airport information
Hobart Airport is a certified airport consisting of one runway. Runway 12/30 was aligned north-west to south-east and was 2,727 m long and 45 m wide. The aircraft movement areas could accommodate aircraft with a wingspan of up to 36 m (such as a Boeing 737).
There were line markings and lights on the runway and turnaround pad to guide pilots in turning and lining up their aircraft for departure (Figure 5). The markings and design appeared to be consistent with the requirements of the Civil Aviation Safety Authority Part 139 Manual of Standards.
Figure 5: Illustrations (top) and photograph (bottom) of lights and line guidance at the turnaround pad
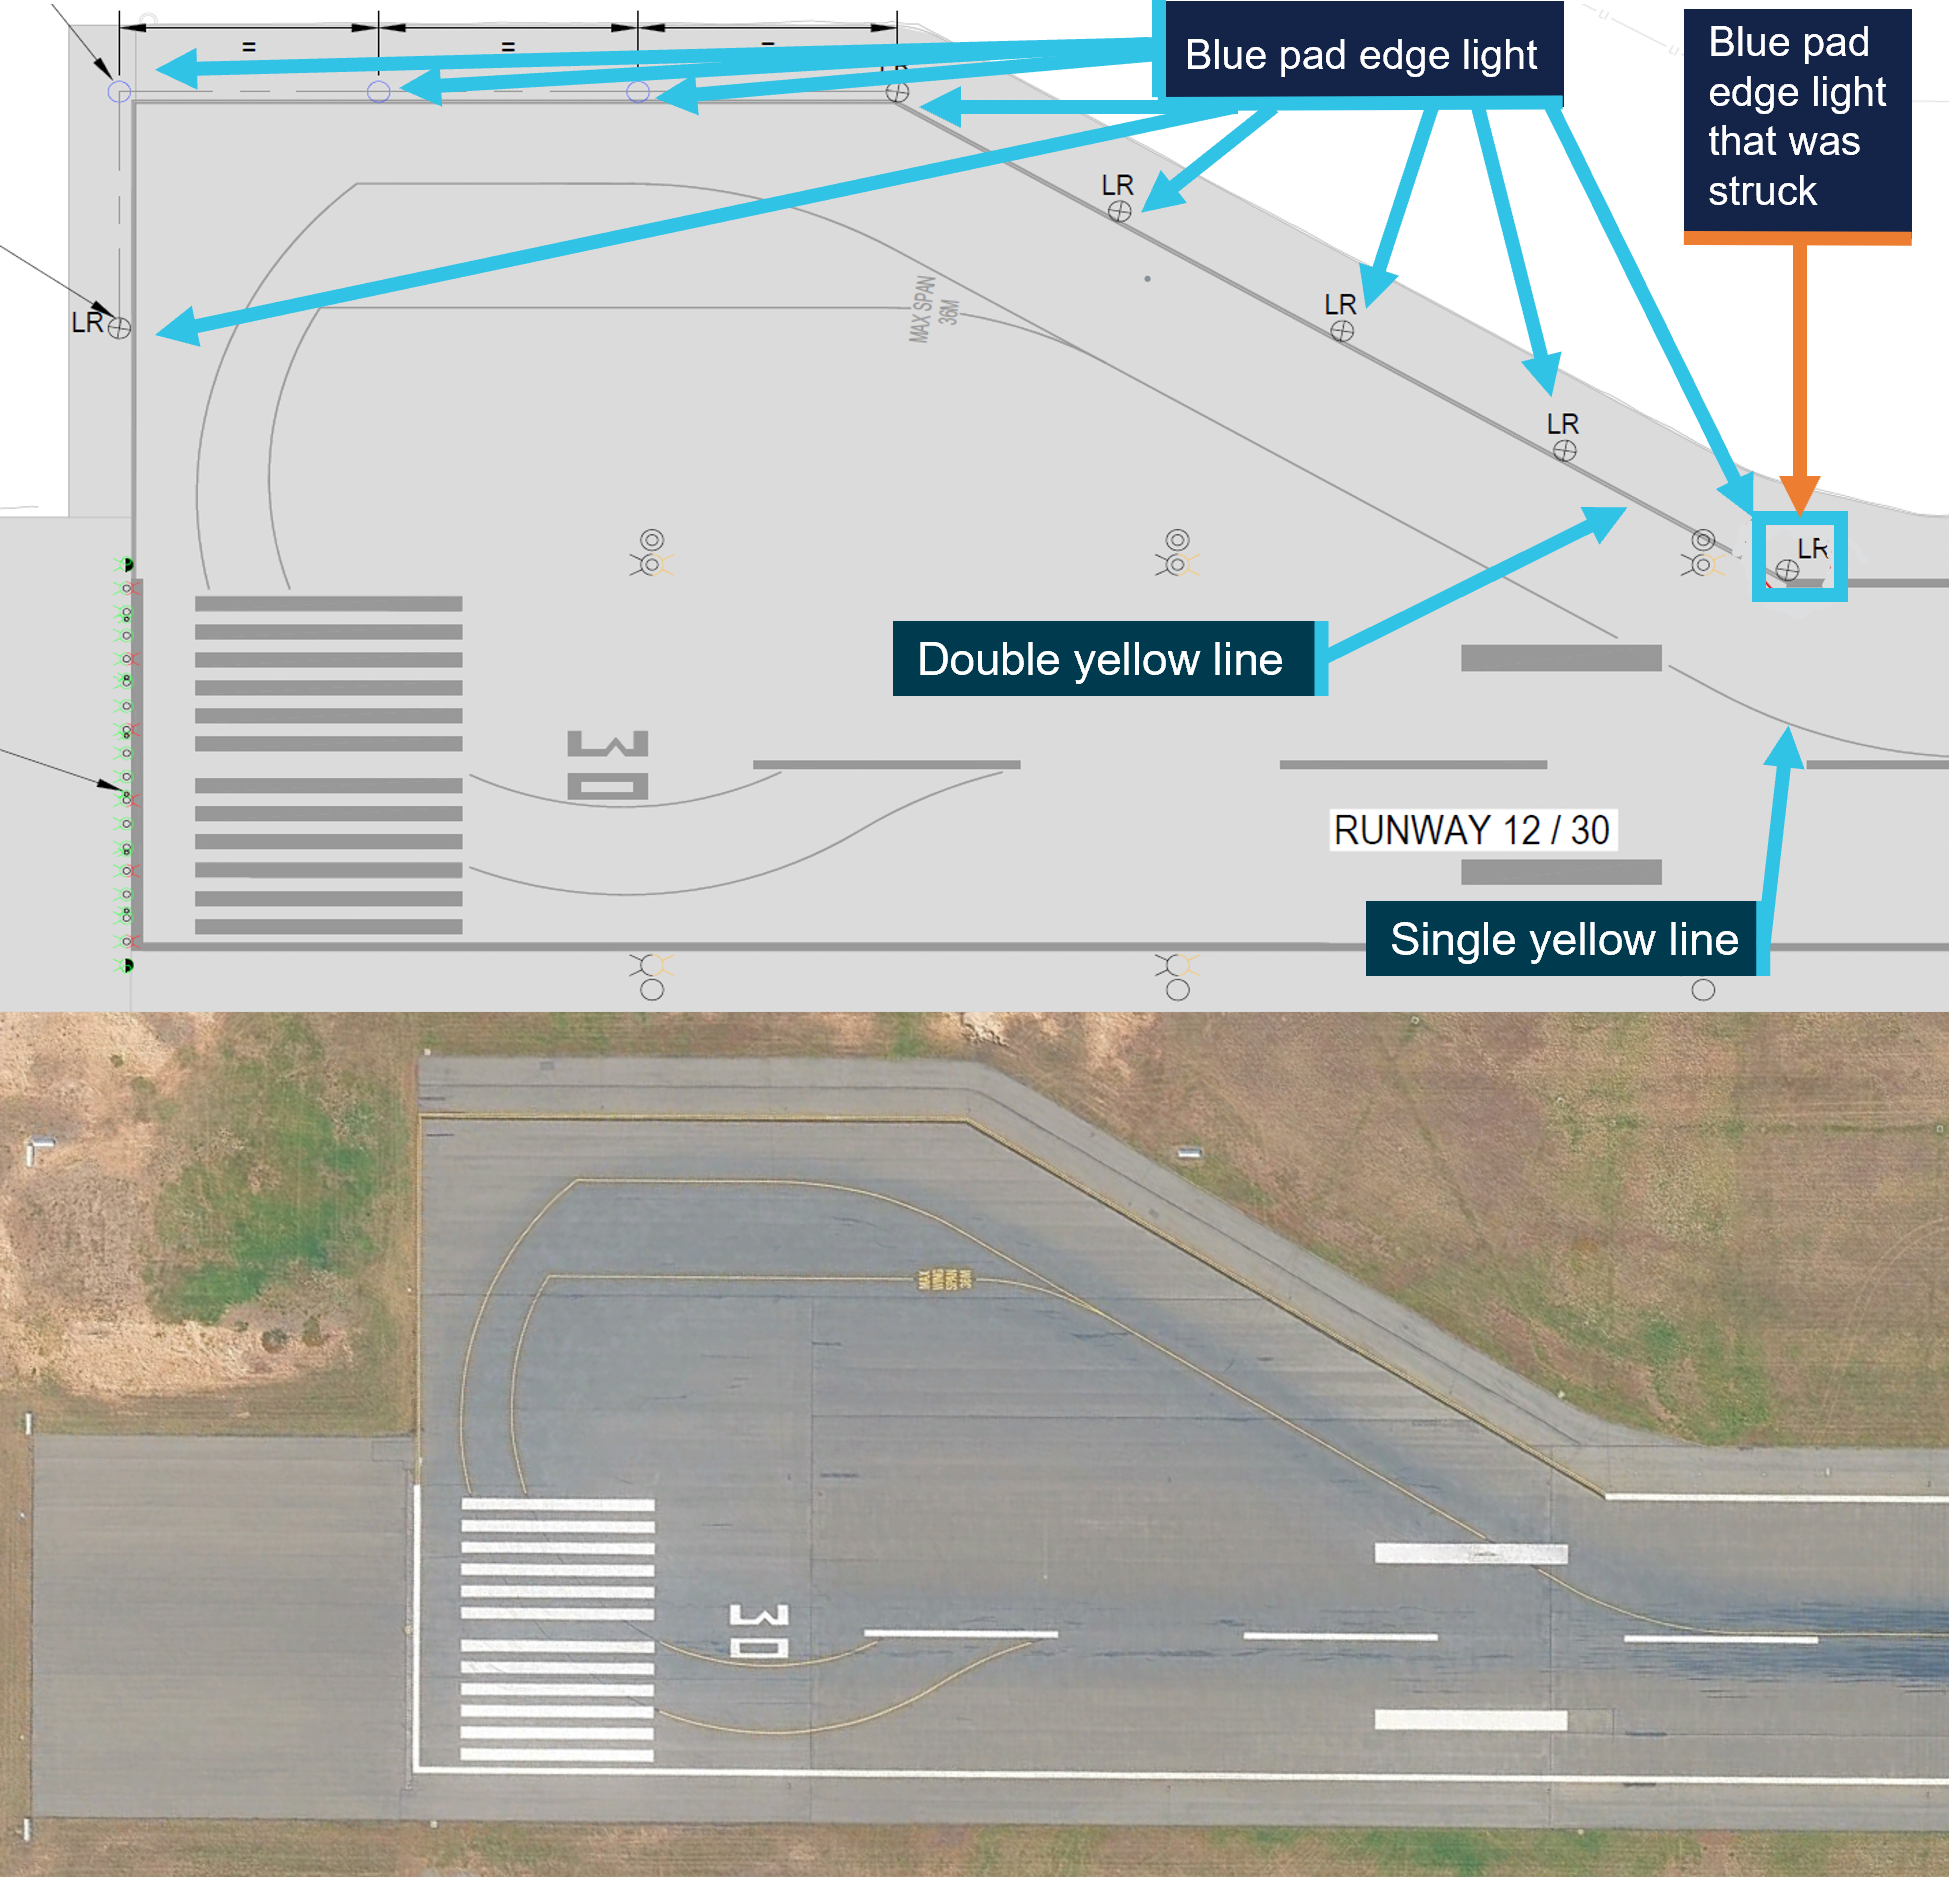
Source: Hobart Airport and Google Earth, annotated by the ATSB
RFDS operational induction
When a new pilot joins the RFDS, the operator carries out a structured induction and training program. Initially, a new pilot undertakes type/class training on the King Air B200 which includes an instrument proficiency check (IPC[5]). Following this training, the new pilot conducts line training flights in the presence of an RFDS supervisory pilot.
The objective of supervised line operations (line training) is to prepare the new pilot for single pilot, unsupervised line operations. The required training outcomes for the new pilot are:
- obtaining the required operational experience
- exposure to and gaining experience of the RFDS’s line operations
- gaining knowledge of the routes and aerodromes used by the AOC.
Whenever an SP occupies one of the pilot seats, they will be the PIC. These policies and procedures are outlined within the RFDS training and checking systems manual.
Training and supervising methodology
Many training methodologies apply the principle of allowing the student to recognise an error and self-correct. This established technique allows the student a chance, and time, to correct themselves, prior to intervention by the instructor or supervisor.
The US Federal Aviation Administration (FAA) Aviation Instructor’s Handbook (2020), which is a recommended reference document for the Civil Aviation Safety Authority’s pilot instructor rating exam, also references this instructional technique. It notes:
Correction of learner errors does not include the practice of taking over from learners immediately when a mistake is made. Safety permitting, it is frequently better to let learners progress part of the way into the mistake and find a way out.
The SP commented that retrospectively, they could have been more assertive and prompter in their intervention once they recognised the proximity of the aircraft to the light.
Safety analysis
Misinterpretation of taxiway/runway visual guidance
While backtracking, the pilot flying (PF) deviated to the right of track in preparation to conduct a wide left turn using the turnaround pad. Making a wide arc turn was a common technique used by pilots for taxiing and turning the King Air B200. As they turned into the turnaround pad, the PF mistakenly manoeuvred the aircraft to align with the blue taxiway edge lights and 2 yellow (edge line) markings. A pilot would normally rely on taxiing guidance of a single yellow line (and green lights), on a taxiway.
The PF was experienced, having held numerous approvals (training and management). However, in this instance, they reported that they subconsciously mistook the taxiway edge lights and double yellow line on the edge of the turning pad as taxi guidance. Observational audit methodologies, such as the Line Operations Safety Audit (LOSA) have demonstrated that crews make on average between one and five errors per flight sector (Thomas & Petrilli, 2004).
Supervisor pilot delayed intervention
The SP monitored the PF’s taxiing path as the aircraft deviated toward the right edge of the runway. This path was initially as expected by the SP reflecting normal operations for turning around using the turnaround pad.
The SP instructed the PF to correct their track when in proximity to the pad edge light, however due to the limited time available and proximity, a strike between the right propeller and taxi light still occurred.
The SP held the belief that the PF was capable, and this assessment may have contributed to delayed intervention, affecting their level of attention when monitoring the taxi path.
The SP adhered to the recognised training techniques in the FAA Aviation Instructor’s Handbook, by allowing the PF a degree of latitude prior to their intervention. However, this action resulted in the SP delaying the intervention and advising the PF of the proximity of the pad edge light, leaving insufficient time to avoid the light.
The SP recognised, retrospectively, that if they had recognised the proximity of the aircraft to the light earlier, they would have been more assertive and more prompt in their intervention.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. These findings should not be read as apportioning blame or liability to any particular organisation or individual. |
From the evidence available, the following findings are made with respect to the propeller strike of a taxiway edge light involving Beechcraft King Air B200C, VH-RFD, at Hobart Airport, Tasmania, on 1 July 2025.
Contributing factors
- The pilot flying misinterpreted the markings and lights at the turnaround pad. This resulted in the pilot taxiing too close to the taxiway edge light, resulting in a propeller striking the light.
- The supervising pilot did not allow enough time to prompt the pilot flying to adjust the taxi route, for the intervention to be effective.
Sources and submissions
Sources of information
The sources of information during the investigation included:
- pilot flying and pilot supervising
- Royal Flying Doctor Service, South Eastern Section
- Hobart Airport
- Civil Aviation Safety Authority
- Airservices Australia
- Bureau of Meteorology
- Flightradar24.
References
Federal Aviation Administration. (2020). Aviation Instructors Handbook. U.S. Department of Transport.
Thomas , M. J., & Petrilli, R. M. (2004). Error Management Training: An investigation of expert pilots’ error management strategies. Adelaide: Centre for Applied Behavioural Science.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
- pilot flying
- pilot supervising
- Royal Flying Doctor Service, South Eastern Section
- Hobart Airport
- Airservices Australia
- Civil Aviation Safety Authority.
A submission was received from Hobart Airport.
The submission was reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigationsThe objective of a safety investigation is to enhance transport safety. This is done through:
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action. About ATSB reportsATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines. Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue. Publishing informationReleased in accordance with section 25 of the Transport Safety Investigation Act 2003 Published by: Australian Transport Safety Bureau © Commonwealth of Australia 2025 
Ownership of intellectual property rights in this publication Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia. Creative Commons licence With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence. The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly. |
[1] A line check is the final pilot’s assessment after line training. After a successful final line check, the pilot is released to a normal line flying operation. See also RFDS operational induction.
[2] The pilot in command (PIC) of an aircraft is the person aboard an aircraft who is ultimately responsible for its operation and safety during flight.
[3] Backtrack. To taxi on a runway-in-use, in the opposite direction to the aircraft’s take-off or landing direction.
[4] Management Pilot means a pilot assigned to management duties
[5] An instrument proficiency check assesses flying skills and operational knowledge, ensuring the capability to exercise the privileges to conduct a flight under the IFR.
Occurrence summary
| Investigation number | AO-2025-034 |
|---|---|
| Occurrence date | 01/07/2025 |
| Location | Hobart Airport |
| State | Tasmania |
| Report release date | 05/12/2025 |
| Report status | Final |
| Investigation level | Short |
| Investigation type | Occurrence Investigation |
| Investigation status | Completed |
| Mode of transport | Aviation |
| Aviation occurrence category | Ground strike |
| Occurrence class | Incident |
| Highest injury level | None |
Aircraft details
| Manufacturer | Beechcraft |
|---|---|
| Model | B200C |
| Registration | VH-RFD |
| Serial number | BL-171 |
| Aircraft operator | Royal Flying Doctor Service (South Eastern Section) |
| Sector | Turboprop |
| Operation type | Part 135 Air transport operations - smaller aeroplanes |
| Departure point | Hobart Airport, Tasmania |
| Destination | Launceston Airport, Tasmania |
| Damage | Minor |
Avalon Airshow accident preliminary report
Video footage from an onboard GoPro camera is aiding the ATSB’s investigation of an aerobatic flight display accident at the Avalon Airshow in March, a preliminary report details.
The Sky Aces display team, comprising four Pitts type aerobatic aircraft operated by Paul Bennet Airshows, was conducting a display during the Australian International Airshow at Avalon Airport, Victoria on the afternoon of 28 March 2025.
One of the aircraft, a Pitts S1‑11X, was performing a solo manoeuvre away from the other three, when it impacted a grassed area to the west of the runway, opposite to the public viewing areas and grandstands.
The aircraft created a 95 m ground scar and debris trail in a south‑south‑westerly direction, before coming to rest upright, facing north, almost opposite to the direction of the impact sequence.
The pilot was seriously injured but was provided first aid before being flown to hospital.
“On being notified of the accident, the ATSB immediately commenced an investigation, with investigators arriving onsite early the following morning to ensure their evidence collection and accident site mapping activities minimised disruption to the airshow flying display,” ATSB Chief Commissioner Angus Mitchell said.
“After it was examined in situ, the aircraft wreckage was transported to a secure hangar on the airport where investigators conducted a thorough engineering examination that found – to the extent possible – no evidence of any control or airframe issues before the accident.”
Mr Mitchell emphasised that the ATSB’s preliminary report does not include findings or analysis, which will be contained in the final report.
Among the evidence gathered is footage from a forward‑facing GoPro camera from the cockpit of the aircraft, which recorded the accident.
It shows the altimeter indicating 100 ft above runway height at the start of the ‘triple avalanche’ manoeuvre – a basic loop with three snap rolls at the top of the loop.
“The pilot had started this manoeuvre at approximately 200 ft above ground level during previous training flights,” Mr Mitchell noted.
Before the camera’s view was blocked by the pilot’s body position, the footage showed the altimeter indicating a height of 700–800 ft just before the aircraft reached its peak altitude, prior to the snap rolls. This was below the pilot's reported normal minimum altitude for commencing the snap rolls of 1,000 ft.
During the back half of the loop, after the snap rolls, the pilot was unable to arrest the rate of descent before the aircraft impacted the ground.
Mr Mitchell said as the investigation continued it would further review video recordings of the accident flight, and consider preparations for the display, as well as aircraft maintenance records and other components recovered from the accident site.
“The investigation is also reviewing display preparations, survivability factors, and the emergency response plan in place at the airport and for the event,” he added.
Read the preliminary report: Collision with terrain involving Pitts S1-11X, VH-PVX, Avalon Airport, Victoria, on 28 March 2025
Crew injury in the engine room of RTM Weipa, 8 km from Gove, Northern Territory, on 23 June 2025
Final report
Report release date: 16/10/2026
Investigation summary
What happened
At about 0800 local time on 23 June 2025, the first engineer and trainee integrated rating of RTM Weipa commenced planned maintenance on the main engine while the ship was at anchor off Gove, Northern Territory. The crew used the engine room overhead gantry crane to handle various machinery components during the maintenance work.
About an hour later, as the planned work progressed, the traversing motor of the gantry crane detached from its overhead mounting and struck the trainee integrated rating, resulting in minor injuries and minor equipment damage.
What the ATSB found
The ATSB found that while external bolts were used to secure all other components on the engine room crane traversing arrangement, the electrical motor was secured to the worm drive gearbox using internal M6 x 30 bolts. These bolts were not externally visible and were only accessible on dismantling the motor from the gearbox. Additionally, the manufacturer’s instruction manual did not adequately identify that the bolts were internal, nor did it provide any instructions for checking the integrity of these bolts during routine preventive maintenance. Consequently, the crew were unaware of the internal nature of these bolts, and the bolts were unchecked during routine inspections. Due to the height and location of the crane traversing arrangement in the engine room, it was also impractical for the ship’s crew to routinely inspect the integrity of these bolts by having to dismantle the motor on each occasion.
The investigation identified that the crane traversing motor was observed to be wobbling about 4 months prior to the incident. However, this defect was incorrectly addressed and reported. It was also evident that shipboard defect reporting practices, in general, were inconsistent and not in accordance with the safety management system. A post-incident shipboard inspection by the ship’s crew identified that the crane’s pinion shaft was also bent. It was likely that the resulting imbalanced operation of the traversing arrangement contributed to the motor’s securing bolts fully undoing themselves over time.
The same model crane was installed across the operator’s fleet of 4 ships. The ATSB identified that none of the ships were fitted with a suitable access platform from where crew could safely undertake preventive maintenance on the crane traversing arrangement. Crew reported using improvised and unsafe access platforms while performing such work at heights, without having implemented the necessary working aloft permits.
What has been done as a result
The crane manufacturer, Sekigahara Seisakusho, has revised its maintenance procedures to ensure that the traversing motors on such cranes are appropriately installed and can be routinely inspected by ships’ crews without equipment disassembly. Sekigahara Seisakusho has also recommended 5-yearly inspections of the crane by a manufacturer-certified technician.
The ship’s manager, ASP Ship Management (ASP), has revised its planned maintenance procedures for the engine room crane in accordance with the manufacturer’s amended guidance. ASP has also installed fixed platforms fitted with safety chains in the engine rooms on its fleet of ships to enable crewmembers to undertake a close-up inspection of the crane’s overhead components.
Formal working at height controls, including permits, risk assessments, safety checks and fall protection measures have been incorporated into maintenance procedures and reinforced through crew training. In addition, ASP has implemented fleetwide training and procedures to ensure defects are correctly recorded, cannot be replaced by informal reporting and it will monitor compliance through ongoing reviews and inspections.
Safety message
The investigation highlights the importance of conducting equipment inspections and maintenance appropriately, as well as ensuring that supporting procedures provide clear, relevant and effective guidance. Where equipment defects are identified, they should be promptly investigated and rectified, with accurate records retained to support long-term traceability and verification.
In addition, ship crews and managers are reminded of the importance of implementing effective risk controls and recognising the hazards that can arise when deviations from safe work procedures become normalised within the workplace.
The occurrence
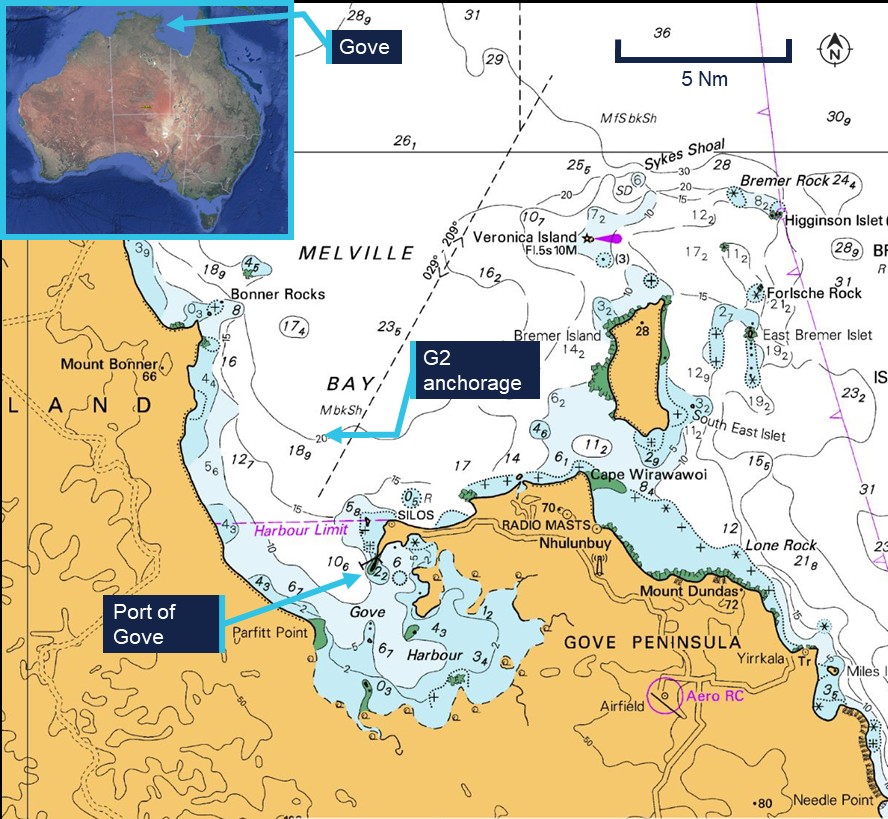
On 22 June 2025, the 236 m bulk carrier RTM Weipa (cover image) arrived at Gove, Northern Territory, following a voyage from Gladstone, Queensland. The ship anchored at the Gove G2 anchorage (Figure 1), awaiting berth availability for cargo loading.
Figure 1: Port of Gove
At 0700 on 23 June, the ship’s management team comprising the master, chief officer, chief engineer and first engineer held a daily work planning meeting with senior ratings in the ship’s office. Amongst other items, the crew discussed the planned overhauling of main engine cylinder unit number 2, which required removing the cylinder head and piston assembly and replacing them with overhauled spare parts. The engine room crew intended to use the engine room overhead gantry crane to move and handle the parts required for the task.
During the toolbox meeting at about 0800, the involved engine room personnel assessed weather conditions to be calm and suitable for the job. They then completed the necessary documentation, which included a lifting plan, risk assessment and permits to work. The work site was marked with appropriate signage indicating the intended lifting operations and restricted entry to non-essential personnel.
At about 0815, a team comprising the first engineer and trainee integrated rating (TIR) commenced disconnecting piping and preparing the cylinder head and exhaust valve for removal from number 2 unit. At about this time, the overhead gantry crane was released from its parked position at the forward section of the engine room and moved to the work site. About half an hour later, the first engineer and TIR were standing on the main engine platform, where they had disconnected a high-pressure hydraulic oil pipe. The first engineer operated the crane using the remote control and moved the pipe a safe distance away, while the TIR handled the crane hook and lifting slings.
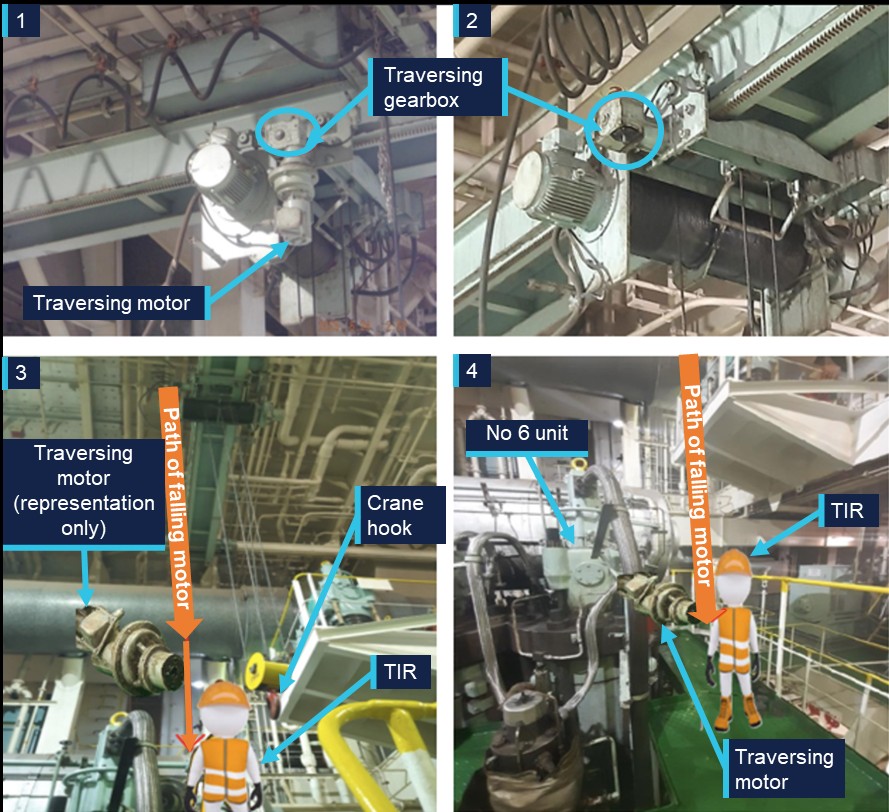
By about 0900, the crew had set the pipe down on the platform, taking the load off the crane. The first engineer stopped the crane’s movement to allow the TIR to take the sling off the crane hook, which was positioned at shoulder height. As the TIR leaned forward to grab the hook, the crane’s traversing motor (about 6 m above) fell and struck the TIR obliquely on their back (Figure 2). The TIR fell to their knees from the sudden impact.
Work was immediately stopped and the first engineer attended to the TIR to determine the extent of their injuries. The TIR was escorted to the control room for a medical assessment and treatment. They were found to have suffered a minor abrasion and some soreness to their back from the impact. The ship’s crew administered first aid, with the application of ice packs to the affected area.
The engineers checked for damage around the incident site. The detached motor was found wedged between the cylinder head and a fuel pipe on main engine unit number 6, crushing the pipe. The motor’s electrical cable had also been pulled out from its connection.
Figure 2: Incident representation (illustrative purposes only)
By 0905, the engine room crew had isolated and tagged the crane out of service. The crew notified the chief engineer, who arrived in the engine room a few minutes later. The chief engineer checked on the TIR and was briefed in detail about the incident. Realising its severity, the chief engineer informed the master.
The chief engineer and master then went to the engine room, where the engine room crew explained the incident sequence to the master. After assessing the TIR’s condition, the master returned to their office briefly and reported the incident to the ship’s shore‑based manager, ASP Ship Management. The master also organised a remote medical assessment of the TIR through Rescue Coordination Centre (RCC) Australia.
At 1045, the master called an emergency safety meeting, where all crew on board were briefed on the serious incident. Thereafter, further safety checks were performed on the engine room crane, which visually appeared safe. An incident investigation was commenced jointly by the ship’s crew and ASP Ship Management.
Context
RTM Weipa
General details
RTM Weipa was built in 2008 by Namura Shipbuilding, Japan. At the time of the incident, the ship was registered in Singapore and classed with Lloyds Register. It was owned by Rio Tinto Shipping and was one of 4 bulk carriers managed by ASP Ship Management (ASP). In addition, 3 Rio Tinto Shipping-owned sister ships were managed by another company, Anglo-Eastern Maritime Services (AEMS).
The ship had an overall length of 236 m, a moulded breadth of 43 m and a depth of 19.5 m. At its summer draft of 13.22 m, it had a deadweight of 93,977 t. Propulsive power was provided by a Hitachi B&W 6S60MC-C MK7 13,500 kW main engine that drove a single, right-handed, five-bladed fixed pitch propeller. The ship had a service speed of 13.5 knots at 87 RPM.
RTM Weipa had been on a fixed trading route along the Australian coast. The ship frequented the load ports of Amrun and Gove, with Gladstone being its regular port of discharge.
Crew
At the time of the incident, RTM Weipa had a crew of 17, including the master. The dedicated engine room complement comprised a chief engineer, first engineer, second engineer and third engineer. Other crewmembers included a chief integrated rating, 4 integrated ratings and 2 trainee integrated ratings.1
The chief engineer had worked on Rio Tinto Shipping-owned ships since 2018, which included previous brief assignments as chief engineer on RTM Weipa in 2018, and 2023. They had re-joined the RTM Weipa about 12 days prior to the incident.
The first engineer had undertaken their cadetship with Rio Tinto Shipping in 2019. Since then, they had worked on several company ships in ascending capacities, with most of their assignments on RTM Weipa. This was the first engineer’s second assignment at that rank, and they had re-joined RTM Weipa 8 days prior to the incident.
The trainee integrated rating (TIR) injured during the incident had commenced their seagoing career with Rio Tinto Shipping in 2024. This was their first tenure on RTM Weipa. At the time of incident, they had been on board for 72 days.
Engine room gantry crane
RTM Weipa’s engine room was fitted with an electrically-powered overhead gantry crane with a safe working load (SWL) of 3.5 t. The crane was manufactured by Sekigahara Seisakusho, Japan. Since 1995, Sekigahara Seisakusho had installed more than 1,800 such cranes in ships' engine rooms.
The crane was routinely used for various engine room maintenance tasks. The crane hook could travel up to 15.6 m in the fore and aft direction and traverse up to 5.86 m athwartships.2 The crane could lift loads through a maximum height of 13 m. For each of these 3 movements, the crane was fitted with a separate electrical motor and drive assembly.
The crane had last been load tested during the ship’s dry docking in Qingdao, China, on 23 August 2023. Thereafter, the engine room crane had been subjected to an annual examination during a routine class survey by Lloyd’s Register in August 2024.3 The crane was certified by the classification society as satisfactory at the time.
Traversing arrangement
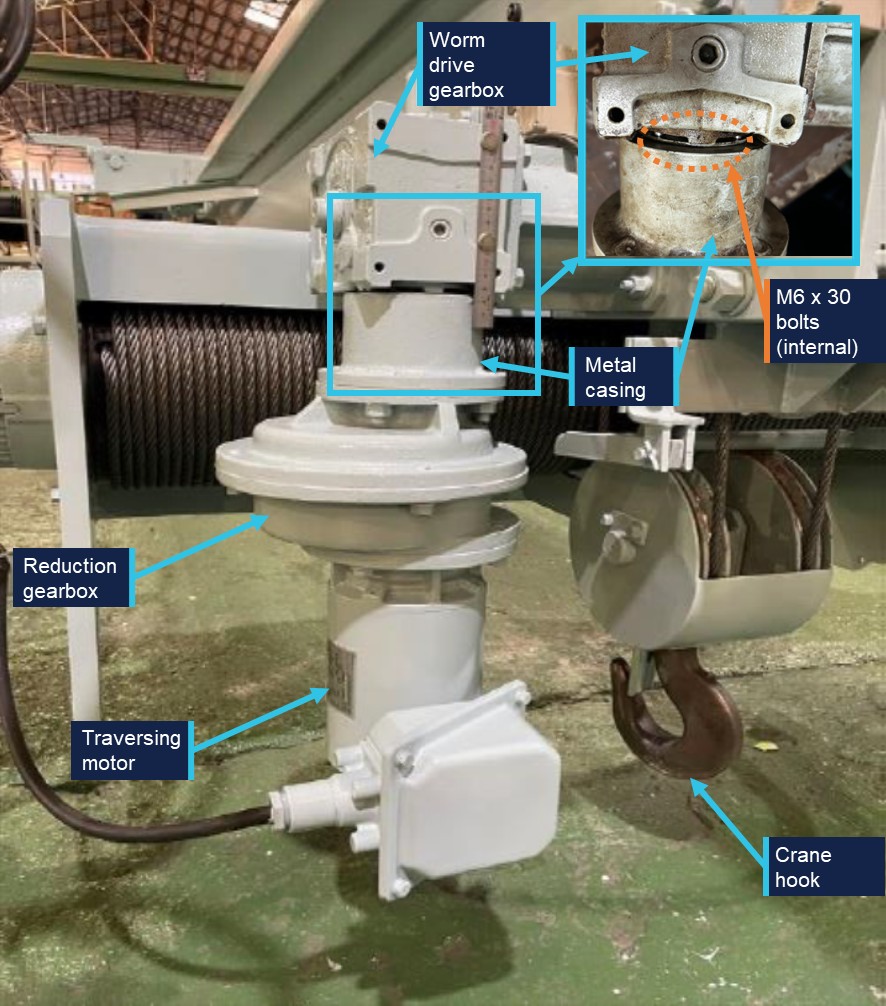
The crane’s traversing arrangement comprised an undermounted 0.75 kW electric motor, weighing about 25 kg. The motor powered a right-angled worm drive gear, which facilitated the athwartship movement of the crane hook via a rack and pinion assembly. A reduction gearbox and a metal adaptor casing installed between the electric motor and the worm drive gearbox made up the arrangement (Figure 3).
Figure 3: Engine room crane traversing arrangement schematic – manufacturer supplied colour‑coded view (above) and extract from instruction manual (below)
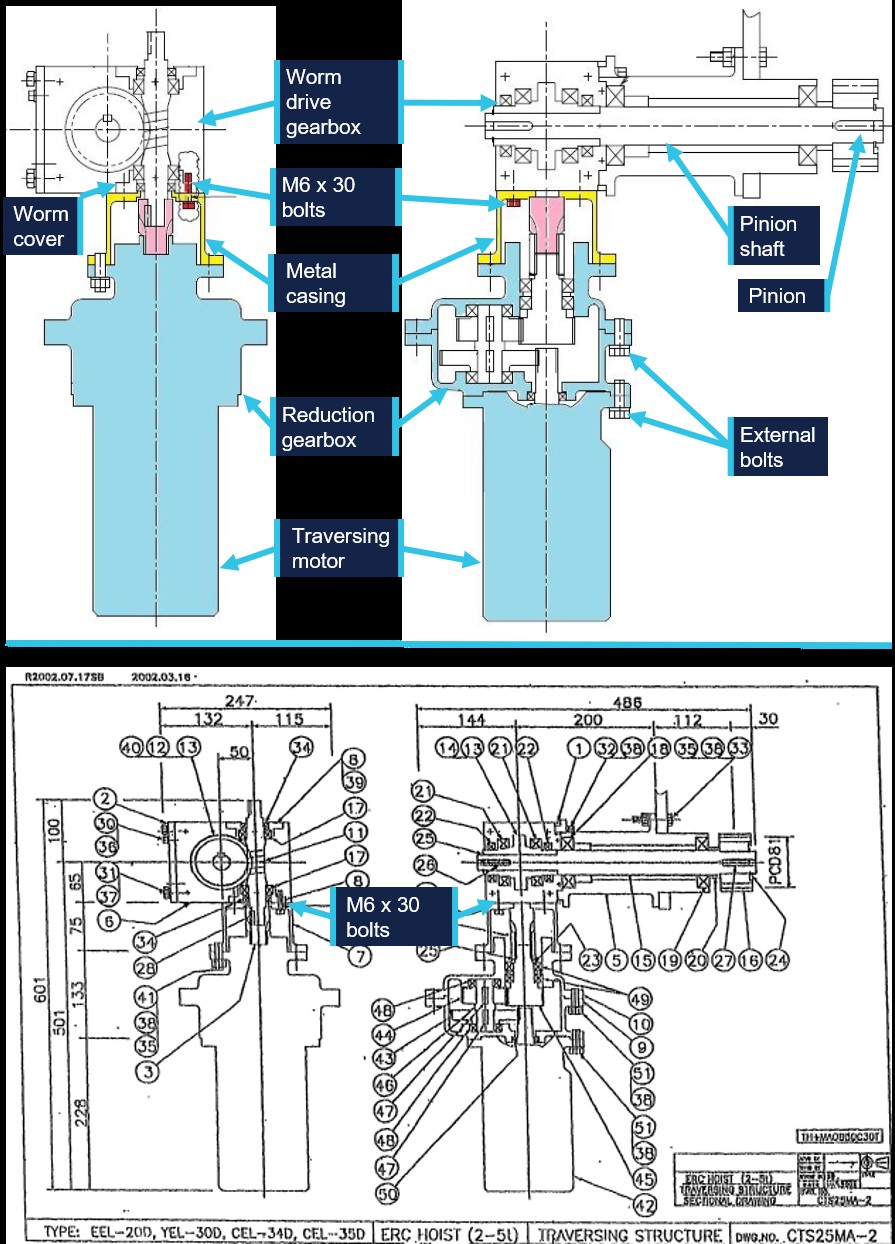
Most components of the traversing arrangement were connected to each other by externally accessible (and visible) bolts and nuts. The connection between the metal adaptor casing and the worm drive gearbox was made using 4 SCM435 grade M6 x 30 mm bolts fitted with spring washers.4 The bolts were first fed through the metal casing, then through a cover plate for the worm gear, and finally fastened into threaded blind holes in the worm drive gearbox (Figure 4).
Figure 4: Internal securing arrangement of engine room crane traversing motor
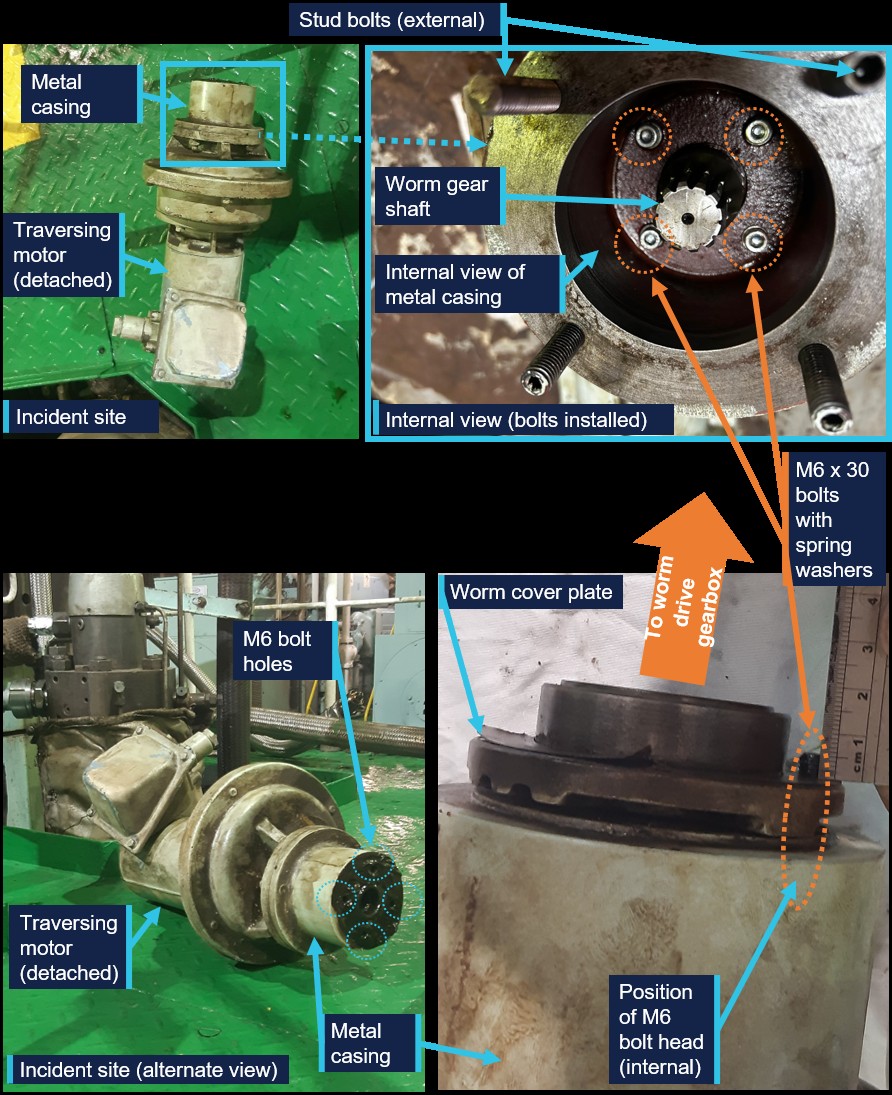
In the crane’s normal working condition, these bolts were not visible as they were contained internally within the metal casing, situated high above the working areas. In order to access these bolts, the reduction gearbox required to be disconnected from the metal casing (Figure 5).
Figure 5: Engine room crane traversing arrangement (assembled view)
Maintenance
The manufacturer’s instruction manual prescribed an inspection regime for various components of the crane, including detail of the inspections required and the corresponding time intervals. With respect to the ‘traversing device’, the manual recommended that each set of bolts be subjected to a ‘hammer test’ at 2-monthly intervals.5 The instruction manual’s maintenance procedures did not provide any specific checks to be performed on the traversing motor’s internal securing bolts.
Planned maintenance system
The ship’s managers, ASP Ship Management (ASP) implemented Star IPS as the planned maintenance system (PMS) across its fleet. The PMS provided a scheduled maintenance plan to ships’ crews for preventive maintenance tasks on various shipboard equipment. In addition, the PMS also enabled users to independently report defects of onboard equipment and machinery. This system facilitated remote access by ASP’s shore-based superintendents to monitor or interrogate tasks and defects.
RTM Weipa’s PMS required that various components of the crane, including the traversing gear and teeth, were to be inspected at 3-monthly intervals by the ship’s crew. However, the PMS did not specify the nature of the inspection checks. A review of the ship’s PMS records since April 2024 indicated that the crew had inspected the engine room crane in May 2025, January 2025 and October 2024. No defects or deficiencies were recorded during these inspections.
The 4 internal securing bolts for the crane traversing motor were not included in standard preventive maintenance checks or schedules. Additionally, there were no historical records available for the complete overhaul of the crane traversing arrangement, including removal of the traversing motor.
Maintenance and inspection access
The ship’s crew and ASP reported that access to the crane’s traversing arrangement was cumbersome due to its height. Evidence provided to the ATSB immediately after the incident indicated that the only means of access comprised the following 2-tier arrangement in the forward section of the engine room:
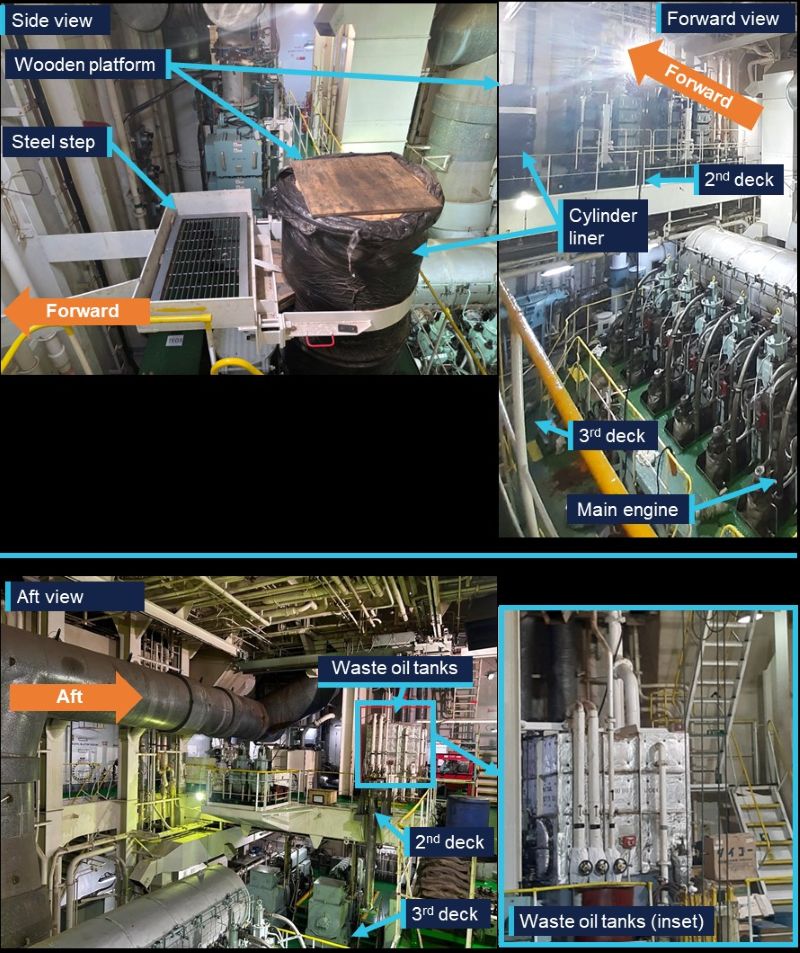
- a fixed step consisting of horizontal steel grating placed on an angular frame, about 2.5 m above the engine room second deck
- an improvised platform consisting of wooden sheets screwed on top of a spare cylinder liner, slightly higher than and adjacent to the fixed steel step.
Neither the steel step nor wooden platform were fitted with any protective guard rails or chains, and the drop from the platform to the third deck directly below it was 7.5 m (Figure 6). The crew reported that while this arrangement facilitated a convenient location for a close-up visual inspection of the traversing mechanism, it did not provide a suitable location for comprehensive inspection or maintenance. The ASP-managed sister ships of RTM Weipa had similar access limitations.
Subsequently, ASP advised the ATSB that the above arrangement was not used by the crew as they only visually inspected the traversing motor and gearbox from accessible areas at deck level. Crew accessed other high sections of the crane, such as the hoisting motor brake and gearbox by climbing to the top of a waste oil tank, in the aft section of the engine room (Figure 6).
Figure 6: View of engine room – crane access arrangements
The ship’s manager also reported that the crew completed daily work plans, work permits and a job safety analysis (JSA) when carrying out any crane maintenance activity in accordance with the ship’s safety management system (see the section titled Safety management system).
Following a review of the ship’s records for the 3 latest dates of planned maintenance (prior to the incident), the ATSB identified that:
- the daily work plan for the latest activity in May 2025 was not signed
- the work plans had not consistently identified crane isolation and working aloft permits as risk control measures
- while the JSA included the risks of working at heights, working aloft permits were not completed on any occasion.
Equipment modifications
In or about August 2023, following the ship’s departure from drydock, the crane’s limit switch had been relocated to limit its forward travel distance. This was undertaken to prevent the crane traversing assembly from impacting the then newly-installed ballast water treatment system (BWTS), located at the forward end of the engine room second deck (Figure 7).
Figure 7: Engine room crane and ballast water treatment system
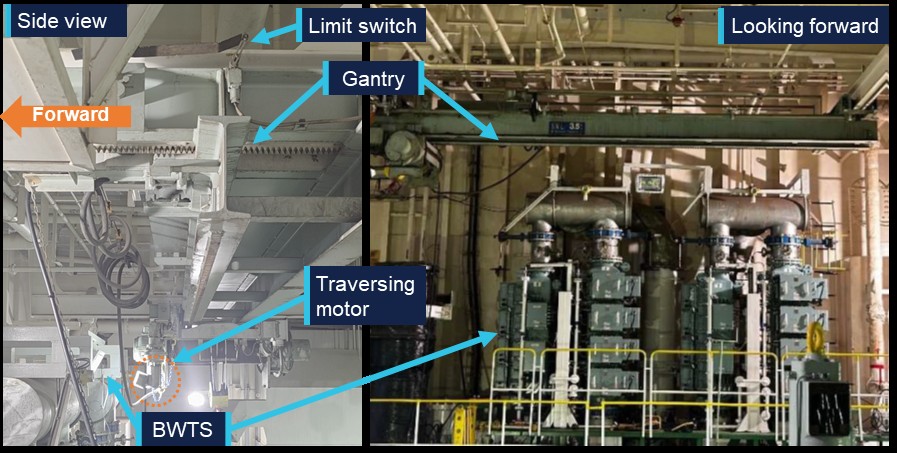
The relocation of the limit switch was not identified as a requirement during the BWTS installation but was later completed after the impact hazard was identified by the ship’s crew. There were no available records confirming the date this was undertaken, nor any reports of actual impact.
Safety management system
The International Safety Management (ISM) Code6 provides the international standard for the safe operation of ships. The objective of the ISM Code is the prevention of human injury or loss of life and the avoidance of damage to the environment and property. To achieve this objective, ASP had implemented a safety management system (SMS) across its fleet.
The SMS included a generic fleetwide publication titled ‘vessel operations manual’ (VOM), which provided policies and procedures, including instructions and guidance for various shipboard operations. It was intended for the VOM to assist ships’ crews with the effective identification and management of hazards to prevent accidents and environmental damage.
While the VOM provided procedures and precautions for lifting appliances such as deck cranes, and separately, certain engine room operations, it did not detail any instructions for the engine room gantry crane. The VOM provided generalised guidance that all lifting equipment was to be inspected and the nominated ‘lifting equipment checklist’ completed prior to use.
The VOM also defined procedures for crew working at heights, which required among others:
- a completed working aloft permit for work undertaken at heights of more than 2 m
- barricading to be erected around the work area and fall zone.
Main engine maintenance pre-checks
On the morning of 23 June, the ship’s crew completed a daily work plan, which included a record of the intended maintenance on main engine unit number 2. The plan identified safety measures, including work permits and checklists to be completed for the task at hand. As such, the crew completed the necessary work permits for the job, including the lifting equipment checklist for the use of the engine room gantry crane.
The lifting equipment checklist recorded that the engine room crew had visually inspected the engine room crane and loose lifting gear prior to use. The checklist also identified the heaviest items to be lifted, which were well below the crane’s rated SWL.
Additionally, the crew also completed a lifting plan and JSA which further identified job‑related hazards and the relevant mitigation measures. The risk of injury to personnel and damage to equipment had been deemed ‘moderate’ in the JSA. The JSA mandated a thorough inspection of the lifting equipment before use as a control measure, which consequently deemed the residual risk rating as ‘low’.
Defect reporting
The VOM defined a technical defect or damage as a ‘defect in or failure in the operation of a part of the ship’s structure or its machinery, equipment or fittings’. The operator’s procedures required that ‘defects or damages’ were reported to shore-based management, and that the issue was recorded in the PMS within 24 hours by the master or chief engineer. The record in the PMS was to contain a brief description of the defect, and the report sent to shore management as soon as practicable.
Defects were also to be recorded in the master’s and chief engineer’s weekly and monthly summary reports, and handover checklists until such time as corrected. These records were to be provided to and reviewed by the ship’s technical manager, to confirm the status of defects on board.
The SMS procedures also required the continued reporting of technical defects in their entirety until formally closed out. Defects could only be deemed ‘closed’ when corrective action was taken and mutually confirmed by the shipboard and shore management. The VOM also included diagrammatic flowcharts to provide simplified guidance on defect recording, reporting and close out processes.
At the time of incident, a total of 8 defects were recorded in the ship’s PMS defect list as pending close out. Six of these defects had been identified as ‘observations’ during a shipboard audit in April 2025 and the other 2 were recorded in May 2025. None of the recorded defects related to the engine room crane.
Crew handover procedures
The SMS included procedures for the handover process between ships’ crewmembers, including documenting a handover by a member of the ship’s management team. ASP required that the handover notes of the shipboard management ranks, which included the first engineer, were to be filed on board and a copy sent to the ship manager ashore. The handover notes were to be structured in accordance with the following general format:
- planned maintenance overdue
- planned maintenance due
- current maintenance
- plant deficiencies
- plant modifications or changes
- plant history over past swing period
- general comments
- joint inspection of plant completed.
The outgoing first engineer was to sign and date the handover notes. Both the outgoing and incoming crewmembers were required to undertake a joint inspection of the engine room and machinery spaces to highlight any issues contained in the notes. On confirming their satisfaction with the information provided, the incoming first engineer would countersign the notes and take over the first engineer’s duties.
Shipboard investigation
Documentation and records
A post-incident review by ASP to identify any previous issues with the engine room crane found that, in February 2025, its traversing motor was recorded as being ‘wobbly’ in the first engineer’s handover notes. The outgoing first engineer had not properly investigated the motor wobble due to its height and location, assuming instead that it was caused by a collapsed tapered roller bearing. A spare bearing was not ordered.
A soft copy of those handover notes, which neither first engineer had signed, was the only one that had been retained on board. No copy of the notes was available in the ASP office ashore. The subsequent handover notes of the first engineer and chief engineer did not report any abnormal crane motor behaviour.
In May 2025, the ship’s engineers raised a spare parts requisition for the crane traversing gear, which included items such as bearings and oil seals. Due to its lead time, the order was scheduled to be delivered to the ship after the incident date.
An ATSB review of shipboard records identified that equipment defects recorded in the chief and first engineers’ handover notes over several months had not been recorded in the PMS as required. These defects included critical equipment such as the rescue boat davit, fuel oil system, and ballast water treatment system.
Separately, a safety concern with the ship’s provisions crane6F that had been escalated to the chief engineer was recorded in the first engineer’s June 2025 handover notes. However, the corresponding information did not feature in the chief engineer’s handover notes that were also completed at the same time.
Equipment inspection
Following the incident, the ship’s engineers inspected the engine room crane. Thereafter, ASP and Rio Tinto Shipping also carried out their inspections. Collectively, the inspections identified that:
- the crew on RTM Weipa and other ASP-managed ships, as well as the shore-based management, had not been aware of the traversing motor’s internal securing arrangement
- the internal bolts had a thread engagement length of approximately 6 mm (Figure 8) and were threaded into blind holes in the worm drive gearbox with limited scope to use longer bolts
- there was negligible damage to the threads of the 4 M6 x 30 bolts and the bolt holes
- two external casing bolts (unrelated to the internal M6 x 30 bolts) were damaged from impact during the motor’s fall
- apart from the above impact damage, no damage was identified to the remaining section of the traversing structure and to adjacent equipment, such as the BWTS
- no evidence of structural damage or stress-related failure was observed on the crane’s hook block, wire rope or control system
- the 40 mm (diameter) horizontal pinion shaft of the traversing gear was bent, with a deflection of approximately 1.5 mm measured between its ends, 405 mm apart.
Figure 8: Securing arrangement for engine room crane traversing motor

Fleetwide investigation
Rio Tinto Shipping and ASP raised fleetwide awareness of this incident and instructed crews to inspect the arrangement on their respective ships. The engine room cranes from the 3 other ASP-managed sister ships across the fleet were confirmed to be satisfactory.
It was also identified that the AEMS shore-based management and their respective ships’ crews were not aware of the traversing motor’s securing arrangement. Upon inspection of the AEMS-managed ships, it was found that the traversing motor securing bolts on one of its ships were ‘approximately three-quarters of a turn loose’. This was only discovered when the motor was opened for inspection. There was no prior indication of the loosened bolts, such as paint damage at the casing joints, motor wobble or impact damage.
ATSB materials analysis
The ATSB obtained the 4 M6 x 30 bolts and conducted a detailed technical analysis of them, finding that:
- The bolts exhibited scoring on the thread flanks of about 4 full threads, which corresponded to an engagement length of 6 mm.
- Based on the bolt specifications, the recommended minimum thread engagement length in blind hole applications for mechanical strength, durability and reliability was about 5.5 to 6.0 mm.7F
- While there was no deformation in the engagement region, the bolts exhibited thread deformation outside the region of engagement.
Safety analysis
Crane motor detachment
Self-loosening of bolts
The engine room gantry crane was stationary with no load on the hook when its traversing motor suddenly detached from the worm drive gearbox and fell. The trainee integrated rating working below received a glancing impact from the motor resulting in minor injury.
The motor was connected to the gearbox by 4 internally mounted bolts. Subsequent examination of the bolts found no overstressing or damage to the engaged threads, indicating that they had loosened over time. The thread deformation observed outside the engagement region was consistent with repeated contact of the bolt threads against the worm cover plate and metal casing, likely following the loosening of the bolts.
There was no record of the motor being disassembled to indicate any history of the bolts loosening. However, the lateral movement of the motor (wobble) 4 months before the incident indicates that one or more bolts were loose. Given the marginal thread engagement of the bolts, the loosening of any bolt would have reduced the overall joint clamping force, making the remaining bolts prone to progressive self-loosening.
Contributing factor The bolts securing the crane traversing motor to the gearbox self-loosened over time until the motor separated from the gearbox. The crewmember working underneath the crane at the time received a glancing impact from the falling motor, resulting in minor injury. |
Imbalanced operation
The location of the crane in the engine room meant that it was subject to machinery vibrations, and to a lesser extent, the ship’s motions in a seaway, while in operation and when parked. In addition, rotational movement coupled with downward acting forces during operation meant that the traversing gearbox and motor assembly were routinely affected by cyclical stresses.
Further, the bent pinion shaft identified during the post-incident inspection likely led to imbalanced operation of the traversing arrangement. This imbalance probably exacerbated movement in the worm-drive gearbox. Left unchecked, ongoing exposure to these recurrent stresses probably contributed to the attached motor’s securing bolts loosening over time.
Contributing factor In addition to cyclical stresses and vibrations during operation, the crane traversing motor was subjected to imbalanced operation due to the bent pinion shaft. This probably resulted in movement of the motor housing and exacerbated the accompanied self-loosening of the securing bolts. |
Defect reporting
Handover process
The crane traversing motor was identified to be wobbling in or around February 2025, about 4 months before the incident. However, the motor was not physically inspected due to its reported inaccessibility. Instead, it was assumed that the wobble was due to a collapsed tapered roller bearing. The wobbling motor was not recorded as a defect item in the ship's planned maintenance system (PMS), nor was this information conveyed to its shore-based management. While the wobble presented an opportunity to investigate the cause of anomalous behaviour of the motor, this was not done. In the absence of an inspection, progressive loosening of the motor went unchecked.
Contributing factor While the ship’s crew identified the crane traversing motor to be wobbling about 4 months before the incident, it was not inspected. Further, the defect was not logged in the ship's planned maintenance system nor reported to the ship’s manager. Therefore, the motor's securing arrangement was not identified, and loosening of the bolts went unchecked. |
Defects oversight
In addition to the crane traversing motor wobble, there was evidence of RTM Weipa’s crew not reporting other equipment defects in the PMS, as required by the safety management system (SMS). Instead, crew routinely recorded such defects in their handover notes. This reduced oversight by other shipboard and shore-based personnel, and overlooked the PMS closed-loop functionality to track allocation of personnel and spare parts, and repair timeframes.
ASP Ship Management (ASP) was required to receive handover notes from management-ranked crew as a secondary oversight mechanism. However, the information reported by different crew in their respective notes was inconsistent. Some handover notes were unsigned, and neither provided to, nor requested by, ASP.
While the crew circumvented the primary defect reporting process through the PMS by reporting defects in their handover notes, the alternate process was also deficient. Consequently, there was no assurance that defects would be adequately addressed, and ASP had limited awareness and oversight of the defects on board its ship.
Contributing factor Shipboard defects were not recorded in the designated planned maintenance system but instead, were routinely conveyed through an ineffectively implemented crew handover process. Consequently, defects were inadequately addressed and ASP Ship Management lacked oversight of any corrective measures required. (Safety issue) |
Inspection and maintenance
Concealed bolts
Due to the crane design, the traversing motor’s securing bolts were concealed. Neither the ship’s crew nor shore management were aware of their internal location until after the incident. Therefore, their inspection was not part of any routine or planned maintenance.
Accessing the bolts required complete disassembly of the lower section of the traversing arrangement. There were no records of the crane motor ever being overhauled, including during the ship’s most recent dry docking, which presented a good opportunity for inspection and maintenance. Consequently, the progressive loosening of the bolts went undetected even after the motor was identified to be wobbling.
Contributing factor The securing bolts of the traversing motor were internally mounted and inaccessible without significant dismantling of the external assembly. Consequently, it was impractical for the ship's crew to inspect the integrity of the securing bolts during routine inspections, and slackening of the bolts went unchecked. |
Manufacturer’s instructions
While the crane manufacturer's instruction manual specified that all bolts in the traversing device were to be checked for looseness with a 'hammer test', this was practical only for externally mounted bolts. The hammer test was not practical for checking the internal bolts securing the underslung traversing motor. Further, the maintenance instructions did not:
- identify that these bolts were internal
- specify that any equipment disassembly was required to access these bolts
- provide any additional specific checks to be undertaken on these bolts.
The ATSB investigation also identified several ships in different companies that were fitted with the same model engine room crane as RTM Weipa, but no one was aware of the bolts. In one case, these bolts were found to be loose when inspected.
Given the common operation of such engine room cranes across the marine industry, the absence of critical component-specific maintenance presented a significant risk to crane users.
Contributing factor The crane manufacturer's maintenance procedures did not identify the traversing motor’s internal securing arrangement nor specify any inspection requirements. This increased the risk of loose fasteners remaining undetected until the motor detached. (Safety issue) |
Access arrangements
The ATSB was provided differing accounts regarding the methods used to access the higher, less readily accessible sections of the crane during preventive maintenance routines. One access arrangement involved a wooden platform attached to the spare cylinder liner, which presented a significant fall risk onto the third deck below. ASP later advised that inspections of the traversing arrangement were conducted from deck level only. While this mitigated the fall hazard, this considerably limited the crew’s ability to undertake detailed inspections of the traversing arrangement. The top of the waste oil tank was another reported access location, however, this too presented trip and fall hazards from height due to various obstructions and an unguarded perimeter.
Although access to the crane traversing arrangement and gantry was routinely required for planned maintenance and was not straightforward, a dedicated, secure platform was not fitted to provide safe access. There was no standard procedure or practice to control safe access via a defined route. The incomplete and inconsistent identification of hazards and application of safety measures, including working aloft permits, indicate that risk controls were not discussed or correctly implemented. Consequently, the risks associated with crew access were normalised and extended across other ASP managed ships, increasing the risk to crewmembers fleetwide.
Contributing factor RTM Weipa and other ships managed by the company had no safe access to the crane traversing arrangement for inspection and maintenance. Further, the elevated access routes used by the crew were unsafe, significantly increasing the risk of injury to crew. (Safety issue) |
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time. These findings should not be read as apportioning blame or liability to any particular organisation or individual. |
From the evidence available, the following findings are made with respect to the crew injury in the engine room of RTM Weipa, 8 km from Gove, Northern Territory, on 23 June 2025.
Contributing factors
- The bolts securing the crane traversing motor to the gearbox self-loosened over time until the motor separated from the gearbox. The crewmember working underneath the crane at the time received a glancing impact from the falling motor, resulting in minor injury.
- In addition to cyclical stresses and vibrations during operation, the crane traversing motor was subjected to imbalanced operation due to the bent pinion shaft. This probably resulted in movement of the motor housing and exacerbated the accompanied self-loosening of the securing bolts.
- While the ship’s crew identified the crane traversing motor to be wobbling about 4 months before the incident, it was not inspected. Further, the defect was not logged in the ship's planned maintenance system nor reported to the ship’s manager. Therefore, the motor's securing arrangement was not identified, and loosening of the bolts went unchecked.
- Shipboard defects were not recorded in the designated planned maintenance system but instead, were routinely conveyed through an ineffectively implemented crew handover process. Consequently, defects were inadequately addressed and ASP Ship Management lacked oversight of any corrective measures required. (Safety issue)
- The securing bolts of the traversing motor were internally mounted and inaccessible without significant dismantling of the external assembly. Consequently, it was impractical for the ship's crew to inspect the integrity of the securing bolts during routine inspections, and slackening of the bolts went unchecked.
- The crane manufacturer's maintenance procedures did not identify the traversing motor’s internal securing arrangement nor specify any inspection requirements. This increased the risk of loose fasteners remaining undetected until the motor detached. (Safety issue)
- RTM Weipa and other ships managed by the company had no safe access to the crane traversing arrangement for inspection and maintenance. Further, the elevated access routes used by the crew were unsafe, significantly increasing the risk of injury to crew. (Safety issue)
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies. Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the marine industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report. All the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation. Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action. |
Defect reporting
Safety issue number: MO-2025-006-SI-01
Safety issue description: Shipboard defects were not recorded in the designated planned maintenance system but instead, were routinely conveyed through an ineffectively implemented crew handover process. Consequently, defects were inadequately addressed and ASP Ship Management lacked oversight of any corrective measures required.
Maintenance procedures
Safety issue number: MO-2025-006-SI-02
Safety issue description: The crane manufacturer's maintenance procedures did not identify the traversing motor’s internal securing arrangement nor specify any inspection requirements. This increased the risk of loose fasteners remaining undetected until the motor detached.
Access arrangements
Safety issue number: MO-2025-006-SI-03
Safety issue description: RTM Weipa and other ships managed by the company had no safe access to the crane traversing arrangement for inspection and maintenance. Further, the elevated access routes used by the crew were unsafe, significantly increasing the risk of injury to crew.
Safety action not associated with an identified safety issue
During the post-incident inspection, RTM Weipa’s engineers straightened the bent pinion shaft. The residual deviation was measured to be approximately 0.75 mm between the shaft ends.
The ship’s chief engineer replaced the crane traversing motor’s original securing bolts with new high tensile bolts, which provided a slightly greater thread engagement of about 8 mm. As per the manufacturer’s instruction, thread locking compound was applied to the bolt threads during reinstallation.
As an added precaution, the ship’s engineers connected the traversing motor to the crane saddle using suspended chain slings, rated to 1 t working load limit (WLL). The crane manufacturer did not raise any objections to the fall preventer mechanism so long as it did not interfere with the crane operation. The ship’s crew also affixed a strongback assembly to the crane traversing motor to replace the casing bolts that were damaged during the incident.
Glossary
| AEMS | Anglo-Eastern Maritime Services |
| ASP | ASP Ship Management |
| BWTS | Ballast water treatment system |
| JSA | Job safety analysis |
| ISM | International Management Code for the Safe Operation of Ships and for Pollution Prevention, 1995, as amended |
| MOC | Management of change |
| PMS | Planned maintenance system |
| RCC | Rescue Coordination Centre |
| SMS | Safety management system |
| SOLAS | The International Convention for the Safety of Life at Sea, 1974, as amended |
| TIR | Trainee integrated rating |
| VOM | Vessel operations manual |
| WLL | Working load limit |
Sources and submissions
Sources of information
The sources of information during the investigation included:
- the master and involved crewmembers of RTM Weipa
- ASP Ship Management, the ship’s manager
- Anglo-Eastern Maritime Services, the manager of similar ships
- Sekigahara Seisakusho, the crane manufacturer.
References
International Maritime Organization, (2018), International Management Code for the Safe Operation of ships and for Pollution Prevention (ISM Code) as amended, IMO, London
International Maritime Organization, (1974), The International Convention for the Safety of Life at Sea (SOLAS), as amended, IMO, London
The Association of German Engineers Standard VDI 2230:2014
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
- Australian Maritime Safety Authority
- the master and involved crewmembers of RTM Weipa
- ASP Ship Management
- the ship’s flag State Administration (Singapore)
- Sekigahara Seisakusho.
Submissions were received from:
- ASP Ship Management
- Sekigahara Seisakusho.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigationsThe objective of an ATSB safety investigation is to improve transport safety through:
In accordance with the TSI Act, the ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action, and cannot apportion blame, assist in determining liability, or, as a general rule, assist in court proceedings. About ATSB reportsATSB safety investigation reports are developed in accordance with ATSB procedures and guidelines, and with regard to applicable international standards and instruments. Reports must include factual material of sufficient weight to support the investigation’s analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. An explanation of terminology used in ATSB investigation reports is available here. Publishing informationReleased in accordance with section 25 of the Transport Safety Investigation Act 2003 Published by: Australian Transport Safety Bureau © Commonwealth of Australia 2026 Ownership of intellectual property rights in this publication Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia. Creative Commons licence 
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence. The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly. |
- ^ Integrated ratings are multi-skilled shipboard ratings, assigned to either deck or engine room duties under the direction of the respective department heads.
- ^ Across the width of the ship, from port to starboard or vice versa.
- ^ In accordance with ILO Convention concerning Occupational Safety and Health in Dock Work (No. 152), 1979.
- ^ Chromium-molybdenum steel alloy (JIS G 4053 standard), property class 12.9, metric thread, 6 mm thread diameter, 30 mm shaft length.
- ^ A non-destructive testing method to identify loose bolts by observing the sound and rebound produced when they are struck with a hammer.
- ^ International Maritime Organization, (2018), International Management Code for the Safe Operation of ships and for Pollution Prevention (ISM Code) as amended, IMO, London.
- ^ A specialised deck crane used to transfer stores and provisions between the ship and the quayside or supply barges.
- ^ The Association of German Engineers Standard VDI 2230:2014.
Occurrence summary
| Investigation number | MO-2025-006 |
|---|---|
| Occurrence date | 23/06/2025 |
| Occurrence time and timezone | 0900 Central Standard Time |
| Location | Port of Gove |
| State | Northern Territory |
| Report release date | 16/10/2026 |
| Report status | Final |
| Investigation type | Occurrence Investigation |
| Investigation phase | Final report: Dissemination |
| Investigation status | Completed |
| Mode of transport | Marine |
| Marine occurrence category | Equipment |
| Occurrence class | Serious Incident |
| Highest injury level | Minor |
Ship details
| Name | RTM Weipa |
|---|---|
| IMO number | 9341938 |
| Ship type | Bulk Carrier |
| Flag | Singapore |
| Classification society | Lloyd's Register |
| Owner | Rio Tinto Shipping |
| Manager | ASP Ship Management |
| Departure point | Gladstone, Queensland |
| Destination | Port of Gove, Northern Territory |
| Injuries | Crew - 1 (Minor) |
| Damage | Minor |