Too steep an approach

ao-2012-070_NEWS.jpg

The risks associated with the handling of an approach to land have been highlighted by the ATSB after a Dash 8’s approach set off its warning system.

The incident occurred on 17 May 2012, when the flight crew of the Dash 8 was conducting a circling approach to Laverton Aerodrome in Western Australia. It departed from Perth as a passenger charter flight, with a flight crew composed of a captain and a first officer. As the crew commenced descent into Laverton, they observed that the weather in the area was mostly clear but there were bands of fog and low stratus cloud in the general vicinity of the aerodrome.

Because of the low cloud, the crew positioned the aircraft to maintain their visual reference with the runway threshold and conducted a circling approach. The resulting final approach, however, required such a high rate of descent that it triggered the aircraft’s Enhanced Ground Proximity Warning System (EGPWS). The crew heard some alerts from the EGPWS and knew they had a high rate of descent, but they did not identify an unstable approach.

...the flight crew did not have an adequate understanding of the aircraft’s EGPWS or the operator’s standard operating procedures in regard to mandatory go-arounds.

The stability of an aircraft’s final approach is an extremely important safety element. As they draw nearer to the runway, pilots need to ensure that their approach fulfils various requirements to achieve a stabilised approach. That includes being on the correct flight path to the runway touchdown point at the correct speed and with the aircraft in the landing configuration. The power setting needs to be appropriate for the aircraft configuration and the rate of descent less than 1,000 ft/min.

“If any of these requirements are not met,” says Dr Stuart Godley, head of the ATSB’s research section, “it constitutes an ‘unstable approach.’ Pilots in that situation should undertake a go-around, and try the approach again. The consequences of not doing so can be severe.” The Flight Safety Foundation cites a lack of go-arounds from unstable approaches as the number one risk factor in approach and landing accidents and the primary cause of runway excursions.

Despite the activation of the EGPWS, the flight crew of the Dash 8 continued their approach and landed safely.

The ATSB investigation found that at the time of the occurrence, the flight crew did not have an adequate understanding of the aircraft’s EGPWS or the operator’s standard operating procedures in regard to mandatory go-arounds.

In response to this occurrence, the operator refined their stabilised approach criteria and formulated a method of incorporating realistic EGPWS warning events in the Dash 8 simulator training program. This incident highlights the importance of crews adhering to standard operating procedures and correctly responding to cockpit warnings.

The issue of handling approaches to land is one of the ATSB’s safety priorities, and it forms part of the SafetyWatch web initiative.

Read the final report: Unstable approach involving de Havilland Canada Dash 8, VH-XFZ, Laverton Aerodrome, Western Australia, on 17 May 2012

Signals passed at danger

The ATSB has identified issues with fatigue management after a train passed three signals without taking any action.

The incident occurred at about 0229 on 30 January 2013, when a work crew was picking up litter on the track at Hurlstone Park. They had arranged for Absolute Signal Blocking (ASB)—a protection measure in which the area controller sets signals at ‘stop’ to prevent rail traffic from entering the affected section. The stop signals are preceded by signals set to ‘caution’, so as to give train drivers enough time to brake and come to a stop at the signal.

At that time, Pacific National freight train 9837 was travelling from Nowra to Orange, crewed by a trainee driver and a more senior co-driver. As the train reached the area of Marrickville, it passed a caution signal but the brakes were not applied as required. Forty seconds later, it passed through a stop signal.

...the ATSB investigation found that the more senior co-driver had inadvertently fallen asleep during the approach to the signals.

Immediately, a visible alert appeared and an alarm sounded at Sydenham signal complex. The area controller broadcast an emergency message ‘9837, stop, stop, stop!’ over the open channel radio to attract the attention of the crew of the train. There was no response. Ten seconds later, the area controller again broadcast the same message, and again there was no response from the train crew.

Meanwhile the work crew picking up litter on the track heard a warning from their lookouts that there was a train coming towards them on the Down Goods line. At this point the train was approximately 300 m away from them. The two members of the work crew on track moved to a safe area behind the platform.

Just before the train passed another stop signal the driver reduced the throttle from power to idle and, shortly after passing the signal, he applied the brakes, bringing the train to a stop.

There had been no injuries or damage, but the ATSB investigation found that the more senior co-driver had inadvertently fallen asleep during the approach to the signals. The trainee driver, in a reduced state of alertness, missed the first signal at caution, and the next signal at stop. He applied the brakes once the train passed the final signal at stop after realising this signal applied to his train.

A number of Pacific National’s policies and procedures were examined to determine if any area of the management or training of the train crew contributed to the incident. Fatigue management, and in particular, over- reliance on the use of bio-mathematical model scores used to roster train crew, was one area where improvement was needed. The ATSB also found that there was an absence of adequate procedures and training for drivers who were performing co-driving duties while coaching trainee drivers.

As a result of the incident Pacific National has undertaken a range of actions to improve its approach to fatigue management and the implementation of fatigue training. They have also commenced a review of ‘signals passed at danger’ risk management processes and training requirements for coach/tutor drivers. A trial has commenced of improved data loggers for the Bulk Rail fleet.

Read the final report: Multiple SPAD by freight train 9837, at Hurlstone Park, New South Wales, on 30 January 2013

Risks of carburettor icing

Ao2013119_news.jpg

On 23 July 2013, a Bell 47G2A helicopter flying on a local photography flight from Lake Manchester, Queensland sustained a total power loss. The pilot conducted an auto-rotation which resulted in a heavy landing, causing substantial damage to the helicopter.

The pilot had taken off from Lake Manchester with the carburettor heat on, as was required for the climb. The pilot also adjusted the carburettor heat as required according to the gauge. At the time of the accident the temperature was 13.5 ˚C and the dew point was 9.1 ˚C. According to the carburettor icing probability chart, these conditions were conducive to carburettor icing.   

When the insurance assessor arrived following the accident, the helicopter was started and performed without fault. No fuel contamination was found and the helicopter was found to have been well maintained and in excellent condition. The insurance assessor considered that the weather conditions may have caused icing of the carburettor. The pilot reported that he would have expected the engine to run roughly if icing was present.

All pilots of aircraft fitted with a carburettor are advised to check weather forecast conditions and know the risk of carburettor icing before each flight. The carburettor icing probability chart is available from the CASA website. The report contains details of other helpful publications on carburettor icing.

Read the final report: Total power loss involving a Bell 47G2A, VH-KHJ, 11 km east of Amberley Airport, Queensland, on 23 July 2013

A glider and a helicopter fly too close

AO2013108_news.jpg

A serious incident which saw a glider and a helicopter come too close to each other shows the dangers and responsibilities that exist at Australia’s non-towered aerodromes.

On 29 June 2013, a Janus glider departed from the Bacchus Marsh aeroplane landing area to conduct a local flight with the pilot and one passenger. At the same time, the pilot of a McDonnell Douglas 500N helicopter was conducting circuits.

The Bacchus Marsh aeroplane landing area is located in uncontrolled airspace and does not have an air traffic control presence. Instead, pilots are responsible for making themselves aware of nearby aircraft and maintaining separation. Key strategies for doing so include making sufficient radio broadcasts so that other pilots know your intention, and maintaining a lookout for other aircraft all times.

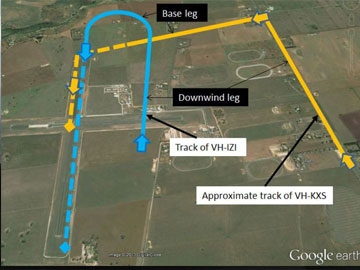
As the pilot of the helicopter flew towards the end of the runway from the east, the glider was flying to the same point from the south.

As the pilot of the helicopter flew towards the end of the runway from the east, the glider was flying to the same point from the south. Both pilots had broadcast calls announcing their intentions on the common traffic advisory frequency (CTAF)

As the glider drew near to the end of the runway, the glider-pilot observed the helicopter ahead and below him, approaching the runway. The glider-pilot estimated that the helicopter passed only about 100 ft below the glider. 

Both pilots reported that they had not heard the other’s broadcasts, and the ATSB investigation could not determine why this might have been the case. The Gliding Federation of Australia found that the limited forward and downward view from the rear seat due to the glider’s natural blind spots and the large frame of the front seat occupant may have affected the pilot’s ability to see the helicopter until it was in close proximity.

The issue of safety at non-towered aerodromes is one of the ATSB’s targeted concerns, and forms part of its SafetyWatch warning initiative. A booklet, A pilot’s guide to staying safe in the vicinity of non-towered aerodromes outlines many of the common problems that occur at non-towered aerodromes, and offers useful strategies for pilots to keep themselves and others safe.

Read the final report: Aircraft proximity event between Janus, VH-IZI, and MD500N, VH-KXS, Bacchus Marsh (ALA), Victoria, on 29 June 2013

Be well informed about weather

AO-2013-063_news.jpg

The ATSB is warning pilots of the dangers of flying over water in low visibility conditions and encouraging pilots to access detailed weather briefings, after four family members died when their aircraft collided with water.

The accident occurred on 1 April 2013, 150 km south-west of Darwin, Northern Territory. A group of pilots were intending to fly various light aircraft from Bullo River homestead to Emkaytee, a private airstrip near Darwin. Their departure was delayed, however, by low cloud. When the group accessed aviation forecasts and weather radar images, they saw that there were isolated thunderstorms, low cloud and rain in the area.

By lunchtime, the weather had lifted at Bullo River, and the weather radar images were indicating improvement along the route. All of the pilots departed between 1300 and 1500, some electing to track via the coast and the rest flying in a more direct route. Among the aircraft was a Cessna 210, carrying a pilot and three family members. That plane would track via the coast.

The group of pilots kept in contact by radio, communicating on a discrete frequency. At about 1510, the pilot of the Cessna 210 reported that he was approaching Cape Ford and the weather ahead was gloomy. He did not sound distressed and at the time no importance was attached to the call. However, that was the last time anyone heard from the Cessna 210.

When the Cessna 210 did not arrive at Emkaytee, search and rescue authorities were notified and some pilots from the group departed in a few aircraft to search the area where the pilot last reported and to check the airstrips in the area.

During the flight from Bullo River to Emkaytee, the pilot continued to track along the planned coastal route towards a thunderstorm, probably encountering conditions such as low cloud, reduced visibility and turbulence, and as a result of one or more of those factors the aircraft descended and collided with water.

Searching in the Cape Ford area was not possible due to continuing storm activity, and fading light forced the return of the search aircraft. The search resumed the next morning until some bodies and a small amount of wreckage from the aircraft were found on the southern part of Anson Bay, about 10 km south-east of Cape Ford. There were no survivors.

The ATSB investigation found that, as the pilot tracked along the planned coastal route, he would have been flying towards a thunderstorm. He would probably have encountered conditions such as low cloud, reduced visibility and turbulence. As a result of one or more of those factors, the aircraft descended and collided with water.

The ATSB is warning pilots of the dangers of flying over water in low visibility conditions and encouraging pilots to access detailed weather briefings, after four family members died when their aircraft collided with water.

When flying in marginal weather conditions, it can be advantageous to track visually via a coastal route. Navigation may be easier, and such a route can ensure an absence of elevated terrain. However, flying over water can mean an increased risk of spatial disorientation when confronted with drastically reduced visibility.

In situations where poor weather is forecast, the ATSB urges pilots to access the Bureau of Meteorology detailed weather briefings to assist with understanding the conditions at the time as well as the immediate trend.

Read the final report: Loss of control and collision with water involving Cessna 210, VH-EFB, 160 km south-west of Darwin, Northern Territory, on 1 April 2013

A fatal wirestrike

AO-2012142_Wirestrike_news.jpg

As it came into land, a Cessna 172N struck a powerline, leaving two people injured and one person dead.

The Australian Transport Safety Bureau has released important advice to pilots and the owners of aeroplane landing areas (ALA) after a fatal accident in Victoria.

On 29 October 2012, a Cessna 172N was flying from Coldstream to a private ALA at Bagshot, Victoria, with a pilot and two passengers on board. As the aircraft approached short final on the approach, its nose landing gear contacted a powerline located at the southern end of the airfield.

The powerline significantly reduced the aircraft’s forward speed, sending the Cessna rotating about its nose and impacting the airstrip in an almost inverted attitude. Almost immediately, a fuel-fed fire began at the wing roots. Witnesses assisted the aircraft occupants from the aircraft, however the pilot was seriously injured and the rear seat passenger sustained minor injuries, while the front-seat passenger had died.

The ATSB found that the pilot had been aware of the powerlines, but that his recollection was that they were closer to the tree line in the area leading up to the landing strip. In addition, a lack of adequate warning markings and the fact that the area leading up to the landing strip was mown led him to believe that the entire strip was useable for landing. This perception, combined with the inherent difficulty of visually detecting wires and the distraction of another recently-landed aircraft on the airstrip, reduced the likelihood of his detecting the wire.

There were no high visibility devices attached to the powerlines, nor were any required under the current Australian Standards.

In response to this accident, the owner of the ALA has made significant changes to the runway markings, landing permission procedures affecting operations at the ALA and the available safety and firefighting equipment. In addition, markers have been erected near the powerline.

The ATSB’s investigation report points ALA-owners to resources that can help them manage the risk of collision with obstacles. It also advises pilots to allow themselves sufficient time to make appropriate decision, and urges them to ensure that everyone in their aircraft is wearing seatbelts correctly, affording the best chance of survival in case of an accident.

Read the final report: Wirestrike involving Cessna 172, VH-TKI, 13 km north-east of Bendigo, Victoria, on 29 October 2012

Stall warnings in high-capacity aircraft: The Australian context 2008 to 2012

Why the ATSB did this research

Stall warning events have always been an area of interest for airlines and aviation safety investigators as they indicate that an aircraft is operating at the margins of safe flight. As these occurrences are reportable to the ATSB, the ATSB can analyse trends across airlines and Australia. By publishing such analysis, it is hoped that the wider aviation industry will be able to learn from the experience of others.

What the ATSB found

A review of 245 stall warnings and stall warning system events reported to the ATSB over a 5–year period showed that almost all were low risk events which were momentary in duration, and were responded to promptly and effectively by the flight crew to ensure positive control of the aircraft was maintained. No occurrences resulted in a stall or an irrecoverable loss of aircraft control, and only a few were associated with minor injuries to passengers or crew (generally those that occurred in severe turbulence) or a temporary control issue.

About 70 per cent of stall warnings reported to the ATSB were genuine warnings of an approaching stall, with the remainder being stall warning system problems. In only a minority of cases were system problems reported that resulted in false or spurious stall warnings such as a stick shaker activation.

Stall warnings (and in particular stick shaker activations) were well reported by Australian air transport operators, and occurred in a range of flight phases and aircraft configurations, not exclusively those related to low speed, high pitch attitude flight, or flight in poor meteorological conditions. Fifty-five per cent occurred in visual (VMC) conditions, and those in instrument (IMC) conditions mostly occurred in cruise. In typical stall warning events during cruise, the aircraft was operating at an altitude where there was a narrow band (about 20 knots) between the maximum operating speed and the stall warning speed (VSW). Common precursors to these events were rapid changes of pitch angle or airspeed. In about one-fifth of these occurrences, the stall warning system was activated when the autopilot tried to correct the aircraft’s speed or flight path due to a disturbance. Stall warnings during VMC flight were most common on approach, often involving aircraft being affected by turbulence while manoeuvring around weather.

The ATSB identified 33 serious and higher risk incidents in which a stall warning occurred. The majority of these involved brief stick shaker activations, and were associated with moderate or severe turbulence. Most happened on approach to land, when aircraft were in a low speed, high angle of attack configuration, and in several cases the stall warning speed was higher than normal (due to a higher wing loading (g) factor in a turn, or an incorrect reference speed switch setting). In these cases, the risk of a stall developing was increased by a lack of awareness of decreasing airspeed and increasing angle of attack prior to the stall warning, and/or an approach to land where the flight crew were focused on trying to correct the approach prior to the stabilised approach height instead of conducting a go-around.

Safety message

Stall warnings occur in normal operations, and are normally low risk events. In Australia, even the most serious events have not resulted in a loss of control, and have been effectively managed by flight crew to prevent a stall from occurring. To avoid higher risk stall warning events, pilots are reminded that they need to be vigilant with their awareness of angle of attack and airspeed, especially during an approach on the limits of being stable.

Publication details

Investigation number AR-2012-172
Publication type Research and Analysis Report
Publication mode Aviation
Publication date 01/11/2013
Subject matter Public transport

Fatal level crossing collision

RO-2013-011_FatalLevelCrossing.jpg

The ATSB is urging drivers to be vigilant at railway level crossings, to observe road warning signs, obey road rules and look out for trains. 

The accident occurred on 19 March 2013 at the Brown Street level crossing in Allansford, Victoria. The El Zorro freight train 9261 was travelling to Warrnambool, Victoria on a scheduled service. 

The level crossing was marked with approach warning signage, road markings and Stop signs for each road approach. Just as the train came to the level crossing, the train’s co-driver, who was seated in the left hand side of the cab, noticed the approaching vehicle. He called out to the train driver to make an emergency brake application. The motor vehicle did not stop at the stop sign, but instead drove onto the level crossing, directly into the path of the freight train, just as the emergency brake was applied. 

The vehicles collided, and the severely damaged motor vehicle came to rest southwest of the level crossing, approximately 33 m from the point of impact. The train continued braking, coming to a stop about 434 m from the level crossing.

The driver of the motor vehicle was fatally injured. Minor damage was sustained by the lead locomotive. There were no injuries to the train crew.

The ATSB found that the south side of the crossing – the direction from which the motor vehicle driver approached the crossing – allowed adequate sighting to the east, the direction from which the train approached. The ATSB concluded that the driver’s familiarity with this crossing, combined with the expectation that a train would not be present due to the low frequency of rail traffic on this line, probably influenced his behaviour.

Warrnambool City Council has temporarily closed the Brown Street Level Crossing until it is equipped with active traffic controls such as lights, bells or boom barriers.

Read the final report: Collision between a motor vehicle and freight train 9261, Brown Street level crossing, Allansford, Victoria, on 19 March 2013

A twist in the Rail

RO2013012_news.jpg

A derailment that spilled about 89 litres of phosphoric acid has shown the critical importance of detecting track defects before they cause an accident.

The derailment occurred on 9 April 2013, near Lowdina in Tasmania. The train, which consisted of five locomotives hauling 28 wagons, was being operated by a single driver. It had departed Burnie that morning, bound for Boyer in Southern Tasmania. 

A few kilometres away from Lowdina, the track made a tight curve to the left, and as the third wagon travelled over the curve, it came into contact with a twist defect in the rails. The leading wheels of the wagon were jolted off the rails, and the rear wheels derailed a few metres later. 

The train continued on, however, with the driver unaware of the derailment of the third wagon. At Lowdina, the derailed wagon struck a set of points, and the impact completely derailed the third wagon, dragging the fourth and fifth wagons off the tracks. The wagons separated and spilled their containers around the adjacent area. The third wagon was carrying two containers of sodium hydrosulphite while the fourth wagon held a tank of phosphoric acid solution.  

The separation caused the train’s brakes to apply automatically, and it stopped about 90 m later. The driver notified the train control centre and TasRail employees were dispatched to the site. Phosphoric acid was discovered leaking from the top hatch of the tank and a number of spill kits were deployed to contain the leak.

Early detection and conscientious management of track defects is critical in maintaining safe rail operations.

It was estimated that about 89 litres of phosphoric acid escaped from the tank, most of which was contained on site. Eventually, the site was declared safe and investigation/recovery operations began. Approximately 800 steel sleepers were replaced along with about 24 m of rail and associated fasteners and switch gear.

The ATSB investigation identified the large twist defect as the cause of the initial derailment, and found it likely that a previously undetected, small to medium sized twist defect had developed under the passage of the train.  

Prior to this incident, the network owner/manager (TasRail) had identified the need to renew the track infrastructure in the area of the derailment and anticipates that the track between Colebrook and Campania should be renewed by June 2014.

The ATSB emphasises to all rail operators that early detection and conscientious management of track defects is critical in maintaining safe rail operations.

Read the final report: Derailment of train 331, near Lowdina, Tasmania, on 9 April 2013

Derailment sends eight train wagons off the track

ro2013006_news.jpg

The ATSB determined that a combination of hot weather and track disturbance activities resulted in a misalignment of the track and a freight train derailment.

The derailment occurred on 12 February 2013 at Locksley, near Seymour in Victoria. The train, an intermodal freight train, was hauling 33 wagons from West Gate Ports, Melbourne through to Harefield in New South Wales. After traversing the Nagambie-Locksley Road level crossing near Locksley, both drivers saw a large track misalignment ahead of them. The driver throttled off from a speed of 108 km/h in an attempt to ride through the misalignment.

Hot weather in the period leading up to the derailment, along with the trains travelling along the track, probably combined with maintenance activities to affect the concentrations of stress within the track, causing it to buckle.

The train continued over the misalignment and travelled a further kilometre, at which time the driver assumed that the train had passed through safely when he noticed a significant reduction in brake pipe pressure—a possible indicator of a train parting or a derailment. The driver brought the train to a halt, then inspected the train and found that the rear eight wagons had derailed. The last three wagons, though still coupled to the train, had progressively dropped away off the track embankment with the last wagon having completely slipped to the bottom of the formation.

The ATSB investigation found that the track misalignment was most likely the cause of the derailment. Investigators identified several factors that would have combined to buckle the track. The quality of the track was already suffering from ballast contamination, which would have weakened its resistance to lateral forces. Hot weather in the period leading up to the derailment, along with the trains travelling along the track, probably combined with maintenance activities to affect the concentrations of stress within the track, causing it to buckle.

As a result of the accident and the investigation, the Australian Rail Track Corporation (ARTC) has initiated several measures to address the problem. Maintenance staff have received additional training, while the track has been tested at 10 sites near the point of derailment. Meanwhile, the ARTC has implemented a ballast remediation program on the Melbourne-Sydney rail corridor.

The ATSB urges all track managers to take the factors of this accident into account when undertaking maintenance and reviewing the condition of their tracks.

Read the final report: Derailment of freight train 3MC1, near Locksley, Victoria, on 12 February 2013





