Importance of flight helmets

The ATSB is reminding pilots, especially those involved in agricultural operations, to wear a correctly fitting helmet to reduce the risk of more serious head injury.

ao2017115_a_news.jpg

On 1 December 2017, the pilot of an M-18A Dromader aircraft was carrying out agricultural spray operations on a paddock north-west of the Emerald Airport in Queensland.

At about 0620, the aircraft was seen completing a spray run and commencing a turn to the right to line up for another spray run. About three quarters through the turn, the aircraft pitched down and the right wing collided with the ground. The aircraft flipped, and come to rest, inverted, facing in the opposite direction about 20-30 m from the initial contact point.

The pilot was able to exit the aircraft and the aircraft was substantially damaged. The ATSB was unable to determine the reason for the aircraft’s downward pitch during the turn. The pilot had no recollection of the accident and no mechanical issue was identified that may have contributed to the accident.

The pilot was wearing his personal flight helmet during the flight.

…pilots involved with agricultural operations are particularly vulnerable to accidents involving major or fatal head injury…

The ATSB found that the pilot’s personnel flight helmet struck the internals of the cockpit and based on the extent of damage to the helmet, it probably prevented the pilot receiving a more serious head injury.

The International Civil Aviation Organization circular Safety in aerial work Part 1. Agricultural Operations(Opens in a new tab/window) discusses the importance of wearing a correctly fitting flight helmet and highlights the pilots involved with agricultural operations are particularly vulnerable to accidents involving major or fatal head injury and the need for a helmet to be part of a pilot’s personal flying equipment.

Read the final report: Collision with terrain involving PZL Warszawa-Okecie M-18A Dromader, VH-WHR, near Emerald Airport, Queensland, on 1 December 2017
Balloon accident injures four

The ATSB is urging pilots to study all available weather information when preparing for a flight. This important safety message comes from the investigation into the hard landing of a balloon that left four people injured.

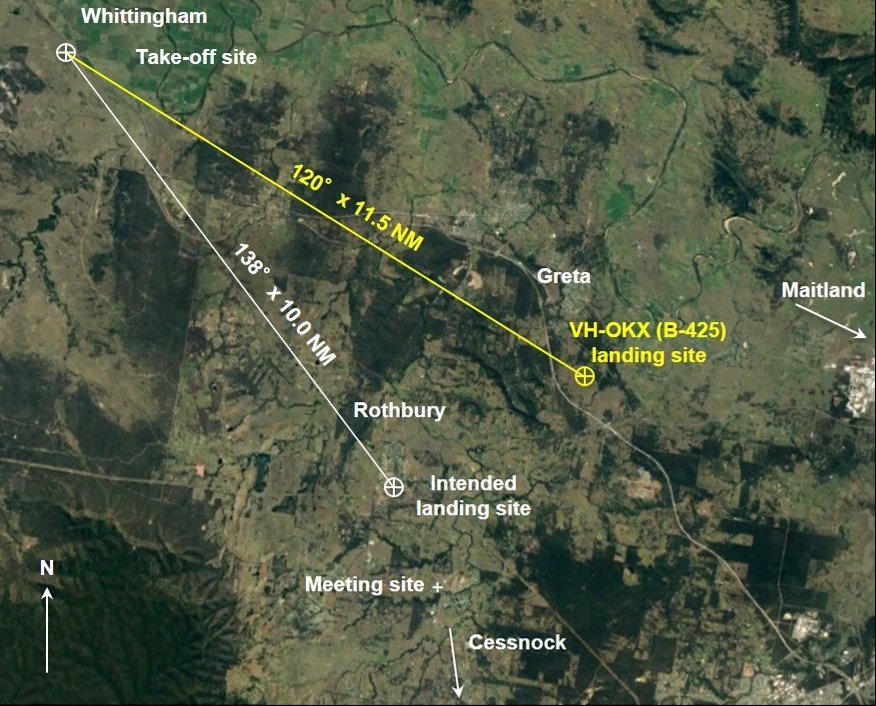
The accident occurred on 13 January 2018, when the International Balloon Flight Company was conducting scenic charter flights in the Hunter Valley, New South Wales, using four of the operator’s balloons. One of the balloons, a Kavanagh B-425 balloon registered VH-OKX, was operating with 15 passengers and one pilot on-board.

In preparation for the flight, the operator had reviewed several weather websites to obtain weather models for the intended flight. Bureau of Meteorology forecasts were reportedly reviewed, but as the forecasts were for the general area, the operator stated the he preferred local weather models for specific areas. He advised that he knew the upper winds were stronger but was confident with the weather model.

Shortly after take-off, the balloons experienced strong winds and turbulent conditions. As a result, the balloon deviated from its intended flight path and landing area.

The pilots of the four balloons communicated with each other regarding the wind speed and decided to land at the first suitable site. The predetermined landing areas were no longer available to them, as the wind change had taken them further east than they had planned. The area selected was a large open field that was not one of their normal landing areas.

The exposure of the pilots and passengers to hazardous weather conditions during the flight, and the injuries sustained during the landing, were avoidable.

The pilot of VH-OKX re-briefed the passengers for landing and advised them to rest their backs on the basket padding and hold onto the internal grab handles.

In light winds, the basket normally remains upright on landing. However, in winds greater than about 10 kt, layover landings can occur. During these landings, the basket tips onto its side and is dragged until the balloon envelope deflates. The baskets are designed to withstand these type of events and have padding and grab handles on the inside of the basket for occupant protection and support. 

Following this landing, the balloon changed direction slightly and was dragged about 40 m towards a large bush in the centre of the field. The side of the basket struck the bush, bouncing it forcefully back into the air. It subsequently came down on one corner and was dragged a further 50-60 m before coming to rest. Due to the significant ground impact forces, one passenger was seriously injured and three others sustained minor injuries.

The ATSB found that the exposure of the pilots and passengers to hazardous weather conditions during the flight, and the injuries sustained during the landing were avoidable and the use of the aviation-specific products generated by the Bureau of Meteorology would have clearly identified the presence of weather that was hazardous to balloon operations.  

Read the final report: Hard landing involving Kavanagh Balloon, B-425, VH-OKX, 4 km south of Greta, New South Wales, on 13 January 2018

Fatigue experiences and culture in Australian commercial air transport pilots

Why the ATSB did the research

Fatigue is an inevitable risk in aviation. As it cannot be completely eliminated, it must be managed. Data on fatigue and its impact on air transport safety is generally only obtained if there is an incident or accident. As a result, there is generally a lack of understanding of the baseline level of fatigue in day-to-day Australian air transport across operators.

To provide the air transport industry, regulators and policy makers with further insights into industry perceptions of fatigue, the ATSB conducted a survey of commercial pilots engaged in passenger, freight, and aeromedical operations in the second half of 2016. To understand the reported level of fatigue during normal operations, the survey aimed to discover the amount of sleep and rest obtained by pilots, as well as their perceptions on the length of rests and duty times. The survey also aimed to capture data on the organisational aspects of fatigue, including how pilots feel about removing themselves from duty because of fatigue experienced and how they think management perceive this behaviour.

What the ATSB found

The majority of survey respondents reported they were sufficiently well rested by the end of their last duty. Over half of pilots reported having 7 hours of sleep or more in the previous 24 hours, and over 60 per cent reported having more than 14 hours in the previous 48 hours, at the end of the last flight. The survey also found a small but significant number of pilots, 10 per cent and 17 per cent, who reported obtaining less than 5 hours of sleep in the previous 24 hours, or less than 12 hours in the previous 48 hours, respectively, at the end of their last flight. These sleep thresholds have been shown to be associated with impaired performance.

Less sleep on duty was more prevalent for international and domestic jet airline pilots than other air transport pilots (regional, charter and aeromedical). While around one third of the respondents reported obtaining the same amount of sleep at home as they did while on duty, around half of international and domestic pilots reported obtaining less hours of sleep on duty than at home. About 15 per cent of international pilots responded they had no rest during their last international flight.

Domestic pilots completed duties on a stand-by day more often than other pilots. Some believed the rest period between duties was too short, duty periods were too long, and access to food during duties was more difficult compared with other pilots, indicating some pilots within this group have negative perceptions of rest opportunities provided by their employers.

Over 90 per cent of pilots indicated their employer offered a formal process for removing themselves from duty due to fatigue. About one third of respondents indicated they removed themselves from duty at least once in the past year, mostly between one and three days. The pilots who removed themselves from duty generally perceived their actions left a negative impression with management (with the exception of aeromedical pilots) and did not feel comfortable doing so.

Safety message

Responsibility to manage the risk of fatigue lies with both the individual pilot and organisation. It is the individual pilot’s responsibility to use rest periods to obtain adequate sleep and to remove themselves from duty if they feel fatigued. It is important for operators to implement policies to reduce the likelihood of fatigue-related issues through rostering practices and by providing an organisational culture where crew can report fatigue in a supportive environment. The results of this research suggest that operating in circumstances conducive to fatigue is an ongoing challenge for a proportion of Australian air transport pilots.

Publication details

Investigation number AR-2015-095
Publication type Research and Analysis Report
Publication mode Aviation
Publication date 22/01/2019
Subject matter Fatigue

A near collision

The ATSB is reminding pilots of the limitations of the see-and-avoid principle, and encourages the use of airborne collision avoidance system (ACAS) technology after two Cessnas were involved in near collision south-west of Darwin Airport on 6 December 2017.

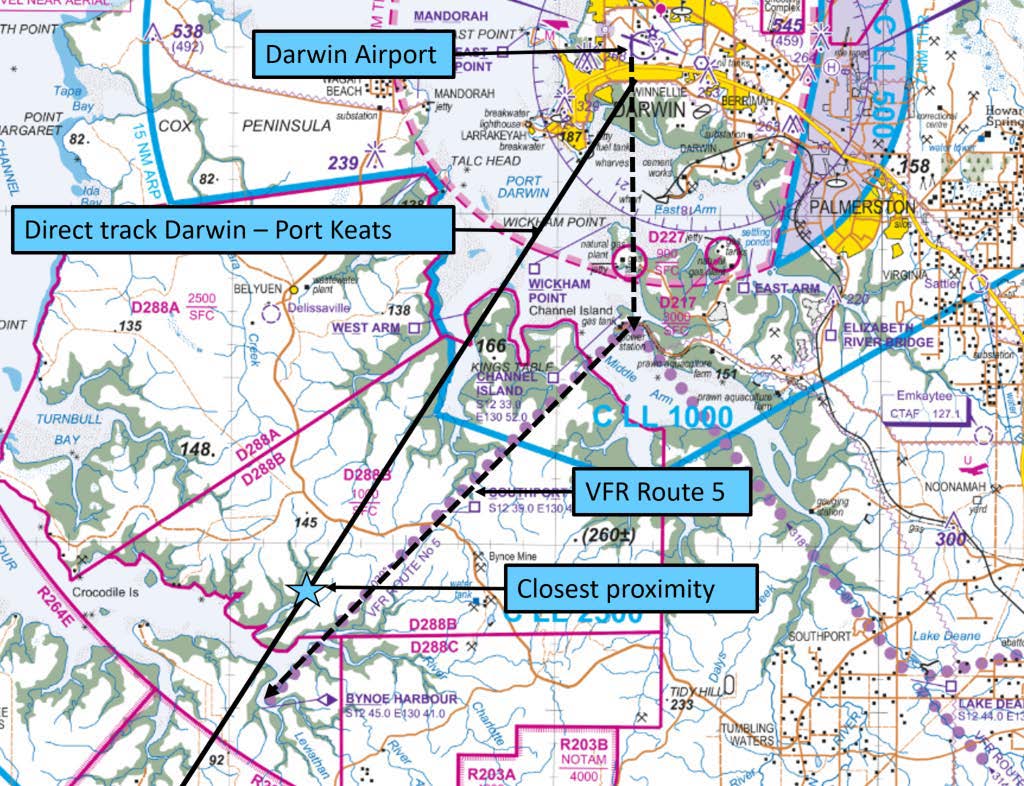
This serious incident occurred, when a Cessna 210 and a Cessna 206, both operating charter flights under Visual Flight Rules (VFR) from Darwin Airport to Port Keats departed in quick succession, and planned to track at 8,500 ft. Air traffic control had advised each pilot of the aircraft’s presence and plans.

The Cessna 210 was the trailing aircraft, but it was travelling faster than the C206. As the two aircraft converged, the pilot of the C210 lost sight of the other aircraft. With the wing structure obscuring the view, the pilot advised air traffic control but took no further action to ensure segregation between the aircraft as they drew nearer.

…the aircraft reportedly came within 5 metres of each other as they passed.

The situation culminated with the aircraft reportedly coming within 5 metres of each other as they passed. Owing to a combination of radar accuracy/resolution and the inaccuracy of the displayed height of the C210, the controller issued a safety alert only after the near collision had already occurred.

While see-and-avoid is the primary means of preventing collisions between VFR aircraft, the limitations of those techniques are well known. Recent advancement of airborne collision avoidance system technologies has made them viable for general aviation aircraft, and they should be considered. They provide valuable information to alert pilots of other aircraft in their proximity and can direct the pilot to take avoiding action, thereby reducing the risk of collision.

This report highlights an ongoing safety issue in aviation. Check out our research report, Limitations of the See-and-Avoid Principle, for more information on this important subject.

Read the final report: Near collision involving Cessna 210, VH-SYT and Cessna 206, VH-HPA, 46 km south-west of Darwin Airport, Northern Territory, on 6 December 2017

Correctly configured

The ATSB’s investigation into the engine failure and forced landing of a Beech Aircraft 76 Duchess highlights the importance of correctly configuring a multi-engine aircraft following an engine failure.

ao-2018-047-final.jpg

The accident occurred on 1 June 2018, when the aircraft was conducting a private flight to Cessnock Airport, NSW, with a pilot and two passengers on board.

During the descent at night, the pilot felt the aircraft yaw toward the right and observed the right engine indications showing a loss of power. The pilot immediately commenced the engine failure checklist and configured the aircraft for single-engine flight. As part of that process, the pilot moved the propeller control to the feather position, but did not confirm that the right propeller had actually feathered. The aircraft could not maintain altitude and continued to descend, even after the pilot increased power on the left engine to maximum.

As the aircraft descended through about 5,500 ft, the pilot calculated it would not be able to clear the high terrain between its position and Cessnock. The pilot declared MAYDAY, and after advising air traffic control, elected to conduct a forced landing.

With no intercom-connected headsets to communicate with the passengers, the pilot did not attempt to warn them of the impending forced landing and focused on flying the aircraft.

The aircraft landed in a grassy field with the landing gear retracted. The pilot and passengers were not injured. However, the aircraft was substantially damaged.

The ATSB investigation found that, after the right engine failed, the propeller was not feathered, or did not feather. The increased drag of the unfeathered propeller prevented the aircraft from maintaining altitude, leading to the necessity of a forced landing.

The report highlights the importance of correctly configuring a multi-engine aircraft following an engine failure, and highlights the recurring safety concern of carburettor icing(Opens in a new tab/window).

The report also confirms the importance of conducting pre-flight passenger safety briefings. In this occurrence, the passengers were not briefed before the flight, nor were they warned about the impending forced landing.

Read the final report: Engine failure and forced landing of Beech Aircraft 76, VH-BDS, 49km north-west of Cessnock Airport, New South Wales, on 1 June 2018

Keep your control

The ATSB’s final report into the wirestrike and collision with terrain of a Cessna 172RG at Parafield Airport, South Australia, is an important reminder for pilots to fly in a controlled manner to increase the likelihood of a successful forced landing.

ao2018050_vh-lcz_news.jpg

On 3 July 2018, the Cessna VH-LCZ was on its final descent for landing. As the aircraft passed through 450 ft, its propeller speed reduced to 1,300 rpm. The pilot turned on the carburettor heat and switched the fuel tank selection from BOTH to LEFT. However, the engine did not respond.

Realising that the aircraft could not maintain enough altitude to reach the runway, the pilot started preparing for a forced landing. The pilot turned towards an unlit area ahead of the aircraft, which he thought was an open space, and pitched the nose of the aircraft down to achieve the optimum glide speed.

As he descended, the pilot heard the sounds of the fuselage striking treetops. The aircraft’s nose wheel then struck a power line and it collided with terrain. The pilot received minor injuries.

The ATSB found that the lack of application of carburettor heat throughout the flight, in conjunction with the weather conditions, which were conducive to severe carburettor icing at descent power, made it likely that the engine failed due to carburettor icing.

When faced with conducting a forced landing, flying in a controlled manner-that is wings level and the aircraft positioned to achieve the optimum glide speed- can improve your chances of surviving a forced landing.

The ATSB reminds pilots to maintain awareness of the weather conditions that are conducive to carburettor ice formation and to closely monitor their aircraft performance during times when the risk exists.

When faced with conducting a forced landing, flying in a controlled manner – wings level and the aircraft positioned to achieve the optimum glide speed – can improve the chances of surviving a forced landing.

The Civil Aviation Safety Authority’s carburettor icing probability chart(Opens in a new tab/window) is a useful tool to help determine your icing risk.

Read the final report: Wirestrike and collision with terrain involving Cessna 172RG, VH-LCZ, Parafield Airport, South Australia, on 3 July 2018

Steep continuous descents

The ATSB is reminding freight operators of the need to ensure train drivers receive regular training and competency assessments on how to operate on steep continuous gradient rail routes.

runawaytrain_ro2017001_news.jpg

On 22 April 2017, a Qube Logistics grain train was travelling from Bogan Gate to Port Kembla, NSW. During its descent down Illawarra Mountain—one of the steepest descents in the NSW rail network— the driver realised control was lost and advised network control that the train was running away..

The ARTC network controller with the Sydney Train’s controller ensured the train had the ‘full road’ with no rail traffic in its path. Reaching a maximum speed of 107km/h as it rounded a curve approaching Unanderra Station, the train came to a stop once it reached the rising gradient at the Unanderra North Junction.

The ATSB found the methods used to control the train during the descent were not in line with the train handling procedures.

Ten brake applications were made as the train descended the mountain between Dombarton and Unanderra. However, the use of multiple brake applications to try and control the train meant the pneumatic braking system was unable to fully recharge between applications reducing its braking capability. Control over the train was further reduced when its dynamic braking system was rendered inoperative.

The ATSB also found actual mass of the train was 10 per cent heavier than recorded. It is likely that the additional weight placed an extra load on the braking system and affected the handling characteristics of the train.

The incident highlights the need for freight operators to ensure regular training and competency checks of train crews who operate on steep descents. Contingency plans and procedures for the management of runways in this area should be continually reviewed and tested by rail infrastructure managers.

Read the final report: Runaway of grain train 8960, Dombarton to Unanderra, New South Wales, on 22 April 2017

Aircraft performance

The ATSB’s investigation into the fatal accident of an Air Tractor AT-502 revealed several factors that contributed to the tragedy, and the measures that aerial application pilots and operators need to be taking.

ao2016146_news.jpg

The accident occurred on 5 November 2016 at an airstrip at Cryon, NSW. The aircraft was conducting aerial application operations. After commencing the take-off, the aircraft failed to gain any significant altitude, and clipped the top of a fence about 1,300 m beyond the start of the runway. After climbing about 20 feet above the ground, the aircraft descended, and collided with trees and the ground before coming to rest inverted. The pilot was fatally injured, and the aircraft was destroyed by impact forces and a fuel-fed fire.

The ATSB investigation found that the flaps were either never extended or were retracted at some point during the take-off. The reason for the retraction could not be determined, but it significantly degraded the take-off and climb performance. This effect was compounded by the estimated weight of the aircraft, the local temperature and the wind conditions.

The aircraft reached a height above the ground where the reduced benefit of ground effect further degraded the aircraft’s performance. The low height and airspeed precluded the pilot from turning the aircraft towards a clear area, and so the aircraft descended into the trees.

... the aircraft manufacturer is updating the maintenance section of the aircraft owner’s manual to specify that the gatebox and emergency dump controls are to be inspected periodically for condition, function and adjustment.

Recorded data from the aircraft indicated that the pilot had attempted to dump the hopper contents after becoming airborne – a move which would have achieved significant gains in climb performance. However, for unknown reasons, a complete dump was not achieved.

The performance benefits of quickly and significantly reducing an aircraft’s weight means that a proper functioning emergency jettison system to dump the contents of a hopper is vital. Pilots rely on the system in case performance is inadequate, particularly when taking off with a heavy load. Registered operators should ensure adequate ongoing maintenance and regular checks to maintain serviceability of the system.

As a result of the accident, the aircraft manufacturer is updating the maintenance section of the aircraft owner’s manual to specify that the gatebox and emergency dump controls are to be inspected periodically for condition, function and adjustment.

This accident also serves as an important reminder for pilots to monitor weather conditions like temperature and wind and to anticipate the potential adverse effects of local conditions on aircraft performance.

Read the final report: Collision with terrain involving Air Tractor AT-502, VH-LIK, 50 km east of Walgett Airport, New South Wales, on 5 November 2016

Night vision goggles

The release of the ATSB’s report into the terrain awareness warning system alert involving Eurocopter BK-117C-2, VH-SYB,  is reminder for pilots of the limitations of night vision imaging systems (NVIS) and night vision goggles (NVGs).

nightvisiongoggles_news1.jpg

On 26 October, the helicopter took off under night visual flight rules (NVFR) from the Crookwell Medical Helicopter Landing Site with the pilot and aircrew member both wearing NVGs. Shortly after take-off, the helicopter entered unexpected low cloud and the pilot initiated the procedure for an inadvertent entry into instrument meteorological conditions.

As the helicopter’s climb reduced, the pilot lowered the helicopter’s nose to regain airspeed but inadvertently over corrected the pitch angle, triggering a terrain caution alert.  

The ATSB found the pilot was likely distracted, during a period of high workload, by the reflection of the helicopter’s anti-collision light against cloud, which was compounded by the use of NVGs.

Clearer guidance may have led to the conduct of a less risker IFR operation

NVGs can increase a pilot’s ability to see the horizon, terrain and objects, but it is important to remember there are also risks and limitations associated with their use. Ambient light, reflections and even the position of the moon, can reduce their effectiveness. NVG use needs to be supported by clear and robust processes from the operator.

During the investigation, the ATSB found there were also some ambiguities in the operator’s manuals about when to conduct NVFR operations with NVIS versus the use of instrument flight rules. Clearer guidance may have led to the conduct of a less risker instrument flight rules operation.

Information on the proper implementation and use of NVIS with NVGs and their benefits and limitations is available in the ATSB aviation research report Night Vision Goggles in Civil Helicopter Operations.

Read the final report: Terrain awareness warning system alert involving Eurocopter BK 117C-2, VH-SYB, near Crookwell, New South Wales, on 21 October 2016

Detect and treat rail defects

The ATSB is highlighting the importance of the early detection and treatment of defects of rail infrastructure, especially those that could cause a rail facture and lead to derailment.

ro-2017-008_news.jpg

The ATSB’s investigation into the derailment of freight train 1501S, near Dry Creek in South Australia on 28 July 2017, found a vertical split head defect had developed through the centre line of the lower leg rail in the curve approaching Dry Creek South.

The ATSB determined the defect had developed undetected from impurities in the rail during its manufacture. When a preceding train travelled over the defect, it caused a break in the rail that was not obvious – visually – to the crew of the following train 1501S. When 1501S travelled over the break, a 2-metre section of rail fragmented derailing its last three wagons.

Acting ATSB Executive Director Transport Safety, Patrick Hornby said the defect in the rail failed to be detected, despite the previous month’s ultrasonic track inspection.

No follow-up action was triggered by the testing provider as required by the track owner creating a missed opportunity for the detection and possible treatment of a defect

“ATSB investigators found that ultrasonic testing indicated the presence of an anomaly, however these results were attributed to the rail’s poor surface condition and not a potential rail defect,” Mr Hornby said.

“No follow-up action was triggered by the testing provider as required by the track owner, creating a missed opportunity for the detection and possible treatment of the defect.”  

Following the incident, the testing provider reviewed its operational and reporting procedures and the rail owner confirmed the effectiveness of its code of practice for ultrasonic rail testing.

“This incident highlights the importance of maintenance providers reporting testing anomalies, to highlight operational risk and to initiate further action,” Mr Hornby said.

Read the final report: Derailment of freight train 1501S, near Dry Creek, South Australia, on 28 July 2017





