The ATSB is highlighting the precautions necessary for sling load operations after a load unexpectedly fell from a Bell 205 helicopter, striking and seriously injuring a worker on the ground.
The helicopter, registration VH-HUE, was being used for external sling loading operations to move equipment from a staging area near Tantangara Dam to a drilling site about 3 km away, south-east of Talbingo, New South Wales, on 10 January 2019. As the helicopter approached the drop-off site, the load, comprising drill rod racks weighing about 1,200 kg, unexpectedly disconnected from the cargo hook. The falling load struck and seriously injured a loadmaster assisting on the ground.
In the course of investigating the incident, the ATSB examined the slings, shackle and hook, but could not determine the reason for the load being released from the hook. However, the ATSB found that the ground personnel had not been maintaining a safe distance from the load.
This incident highlights the dangers associated with external sling load operations.
“This incident highlights the dangers associated with external sling load operations,” ATSB Director Transport Safety Stuart Macleod said. “Unexpected events can occur, and ground personnel should take care to ensure they maintain their separation from external slung loads that are above head height.”
In this accident, the positioning of the ground personnel, in combination with the significant movement of the load as it contacted the ground, meant that they were exposed to higher risk.
“Each sling load operation can be unique, with different locations, different load shape, and different environmental conditions combining to create different safety considerations,” Mr Macleod said. “As a consequence, clear written procedures and detailed discussions prior to commencement of each operation are essential to ensure that all participants are aware of the unique dangers of the operation.”
A collision between a Cessna Caravan floatplane and a small aluminium boat highlights the importance of scanning and assessing landing areas for potential hazards during amphibious flying.
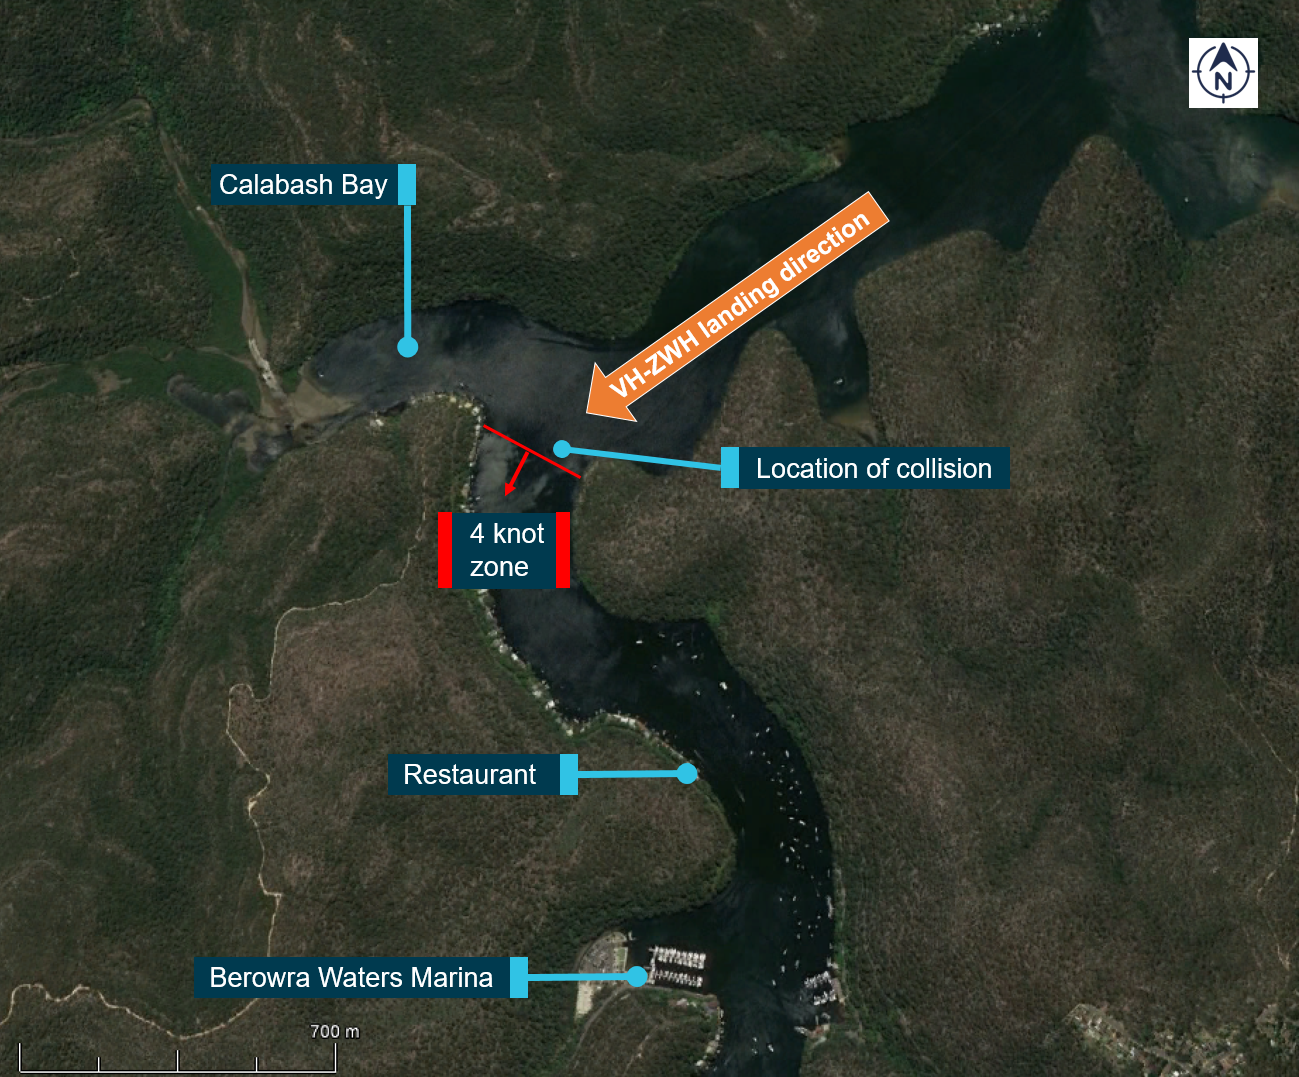
The floatplane had just completed a water landing at Berowra Creek, in the Hawkesbury River catchment north of Sydney, on 29 June 2019. After slowing down to taxi speed, the aircraft’s front left float bumped into a small stationary boat. There was no damage to the aircraft or boat, while one person in the boat sustained minor injuries.
The ATSB’s investigation into the incident found that the pilot did not see the boat due to a combination of factors including the weather conditions on the day as well as the colour, size, lack of movement and location of the boat as it was positioned in the aircraft’s direct path.
This incident highlights the importance of scanning and assessing landing areas for any potential hazards, and of the joint responsibility of both aircraft and marine vessels to see and avoid other aircraft and vessels operating on the water.
“This incident highlights the importance of scanning and assessing landing areas for any potential hazards, and of the joint responsibility of both aircraft and marine vessels to see and avoid other aircraft and vessels operating on the water,” said ATSB Director Transport Safety Dr Stuart Godley.
“When choosing an operating speed for any vessel or aircraft on the water, consideration should be given to any potential blind spots and areas where other vessels could emerge.”
Subsequent to the incident the aircraft operator has advised its pilots to remain on the right hand side of the waterway to reduce the risk of a blind spot near the area of the incident.
In addition, as a standard operation, company pilots are to reduce the speed of the aircraft to an idle power taxi speed after landing, 100 m before the start of the 4-knot zone at Berowra.
The slow-speed collision of an empty passenger train into a buffer stop on 25 February 2019 highlights the importance of train safety systems to protect against driver error and incapacitation, an ATSB investigation notes.
After its passengers had disembarked, Metro Trains Melbourne train TD 6591 departed Newport Station for a siding where it was to be stabled (parked and secured). As the train approached the stabling location, the brakes were not applied in sufficient time to stop the train and it collided with the buffer stop.
The collision resulted in substantial damage to the front of the train and the buffer stop, and the driver was hospitalised with minor injuries.
In subsequent interviews the driver reported losing consciousness for a period of time prior to the collision, recalling entering the siding but having no other recollections until after impact. A subsequent medical examination found the driver may have fainted due to dehydration and lack of nutrition.
Analysis of data from the driver cabin’s Vigilance Control Event Recorder System (VICERS) showed that a brake application consistent with emergency braking was made about 1.5 seconds before impact, but that was after passing the required stopping point.
Train safety systems are an important protection against driver error and incapacitation.
“The driver may have been incapacitated immediately prior to the accident and therefore temporarily lost awareness, leading to the train not stopping at the designated stopping point as the driver did not apply the brakes in sufficient time,” said ATSB Director Transport Safety Dr Stuart Godley.
“However, due to limited and conflicting evidence the cause, duration and presence of incapacitation could not be determined.”
While the train was equipped with a safety system, comprising a pilot valve as part of the master controller, that was designed to apply the brakes in situations such as driver incapacitation, it did not activate in this incident. The recorded data indicated that sufficient pressure was maintained on the master controller, and therefore the only aspect of the train safety system that could have activated and applied the brakes to protect against driver incapacitation was not triggered.
Post-accident testing of the train’s braking system and the master controller hand pilot valve found no faults that would have contributed to a failure to stop.
“Train safety systems are an important protection against driver error and incapacitation,” Dr Godley noted.
“In addition, drivers are reminded to maintain their health and fitness for work to reduce the likelihood of incapacitation including maintaining adequate levels of nutrition and hydration as well as consideration of the potential impact of fatigue,” Dr Godley said.
Information on fatigue is available on the ATSB website.
Incorrectly calculated take-off speeds contributed to an Airbus A320 experiencing flap and landing gear retraction overspeed events,an ATSB investigation has established.
While preparing for a flight from Sydney to Melbourne, the flight crew of the Jetstar Airways A320 were unable to use two electronic flight bags to calculate and check take-off performance data, and instead used manual take-off charts.
But the flight crew inadvertently calculated speeds that were higher than required for the actual aircraft weight and environmental conditions, and those incorrect take-off speeds were not identified by independent verification and cross-checking.
Consequently, the aircraft did not rotate to the correct pitch attitude during its take-off roll, resulting in a higher acceleration rate than anticipated. As a result, the aircraft’s speed at rotation was only 16 knots below the maximum flap extended speed.
Following rotation, the pitch rate remained under the recommended rate, and continued to reduce with the aircraft’s speed increasing. The pilot flying was not alerted to the incorrect pitch attitude rotation; however the pilot monitoring called ‘speed, speed’ to assist in the management of airspeed. The flap extended limit speed was exceeded five seconds after rotation.
This incident highlights the importance of independent validation and crosscheck of flight performance data, in particular performance speeds and aircraft weight.
When alerted to the impending overspeed, the pilot flying reduced the engine power in response, rather than increasing the aircraft pitch. The action of reducing the engine power was taken when the aircraft was below the safe altitude above ground.
Then, climbing through 2,800 feet, the flight crew reported hearing a buffeting noise, and they soon determined that the landing gear was still extended. The pilot flying immediately called ‘gear up’ and the pilot monitoring quickly retracted the landing gear without looking at the speed indication, which was 30 knots above the maximum landing gear retraction speed.
The flight crew discussed the occurrence and with no known adverse indications, they continued the flight to Melbourne without further incident.
“This incident highlights the importance of independent validation and cross-check of flight performance data, in particular performance speeds and aircraft weight,” ATSB Transport Safety Director Dr Stuart Godley said.
The ATSB found that when using the manual take-off charts, the procedure for the calculation for the correct take-off performance speed for the aircraft’s actual total take-off weight was not completed, resulting in a calculated rotation speed based on an aircraft weight significantly heavier than their actual take-off weight.
“This error was not detected through an independent validation crosscheck,” Dr Godley said.
“This investigation emphasises the importance of considering reasonability and accuracy checks, consulting company procedures manuals in the event of electronic flight bag issues, and conducting a normal rotation followed by reference to the Speed Reference System,” Dr Godley said.
A collision involving a track worker and a passenger train at Petrie Station, north of Brisbane, highlights the need for sufficient resources, including time, information about the work environment, train movements and adequate protection to minimise risk to rail workers, a new ATSB investigation report says.
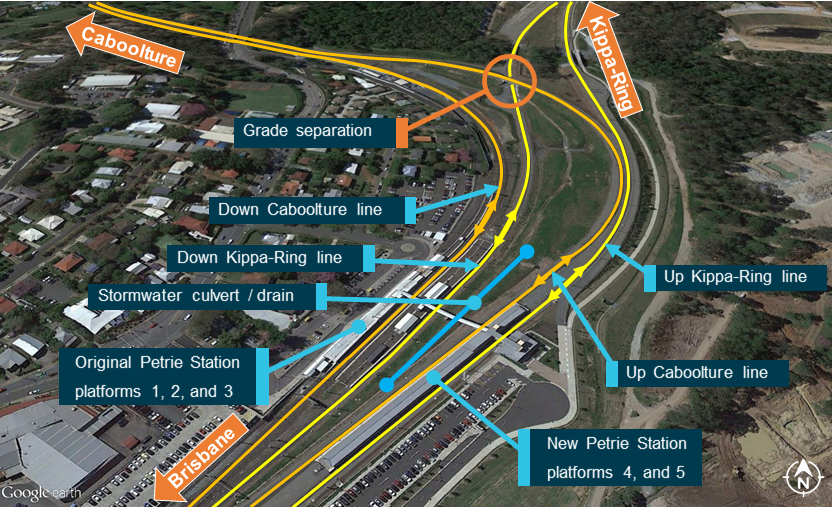
Late in the evening on 29 May 2017, a passenger train approaching Petrie Station from the north struck and fatally injured a Queensland Rail (QR) protection officer. He was part of a team of four protection officers implementing a planned track closure for maintenance of the Kippa-Ring rail corridor from Petrie Station to Kippa-Ring station. The protection officers were using personal continual vigilance (PCV), which requires track workers to see that tracks are clear, frequently look in both directions for approaching rail traffic and not rely on another person to give warning, when walking within three metres of a track (known as the Danger Zone).
The protection officer had placed permanent way protection* to warn approaching train drivers to stop and mark the outer limits of protection for the track maintenance worksite on the Kippa-Ring lines. The collision occurred while the protection officer was walking on the Up Caboolture line, which was open for rail traffic and not part of the track maintenance worksite.
The ATSB’s investigation found that the protection officer did not apply personal continual vigilance techniques while walking within the track Danger Zone. The investigation noted that while it was evident that immediately prior to the collision the protection officer’s attention was diverted by the mobile phone clipped to the front of his shirt illuminating, the protection officer was already in a position of danger with a collision imminent by this point, and the direction he was walking meant that his back was facing the train involved in the collision.
This investigation highlights that to minimise risk, rail organisations should ensure processes relating to track work include provisions for protection officers to have sufficient resources, including time for task, information about the work environment, including train movements, and adequate protection available for the work.
“Although the reasons why the protection officer did not apply continual vigilance techniques could not be determined, it was possible that he had no expectation of rail traffic, and a number of factors that increased risk were identified,” ATSB Director Transport Safety Dr Godley said.
Those factors included time pressures, protection officers not being familiar with the new rail infrastructure layout at Petrie Station for the Kippa-Ring line (which officially opened in October 2016), no processes being in place for ensuring adequate time for protection officers to familiarise themselves with new or changed work sites, and the night shift protection officer supervisor inadvertently marking some open lines as closed on the Train Notice Diagram for Petrie Station that was used by the protection officers. Independent verification of the Train Notice Diagram was not undertaken, and so that error was not identified.
“This investigation highlights that to minimise risk, rail organisations should ensure processes relating to track work include provisions for protection officers to have sufficient resources, including time for task, information about the work environment, including train movements, and adequate protection available for the work,” Dr Godley said.
In response to the accident, QR have commissioned a number of independent reviews on its safe work on track processes and practices, including the use and selection of personal continual vigilance, mobile devices in the rail corridor and its worksite protection compliance inspection systems.
QR have also re-enforced the message of ‘the right to stop work and getting safety right before commencing’ as part of its ongoing network pre-start brief project.
* Permanent way protection:One or more devices approved by Access Providers that provide warning to protect rail traffic crew and workers. The device or devices may be used in conjunction with signalling or blocking facilities.
The loss of 81 containers overboard from the container ship YM Efficiency highlights the importance of safe and effective container stowage planning, an ATSB investigation has found.
Just after midnight on 1 June 2018, the YM Efficiency was steaming slowly into strong gale force winds and very rough seas off Newcastle, en route to Sydney, when it suddenly rolled heavily, causing container stacks to collapse and topple. As a result, 81 containers were lost overboard and a further 62 were damaged, while the ship sustained structural damage to its lashing bridges, superstructure, and accommodation ladder.
Substantial debris from the lost containers subsequently washed ashore on the New South Wales coast. At the time of the ATSB investigation report’s finalisation, search efforts for those containers – including with the use of remote underwater vehicles – had identified 66, with a few having washed ashore or close to shore. Five containers have been removed, and 15 containers have yet to be found.
Source: ATSB
The ATSB investigation determined that the forces generated during the sudden, heavy rolling placed excessive stresses on containers stowed aft of the ship’s accommodation. This resulted in the structural failure of containers and components of the lashing system, leading to the loss of containers overboard.
All potential causes for the sudden rolling were investigated, such as the possibility of an abnormal wave, but there was insufficient evidence to establish a definitive cause.
Further, the condition of the ship’s lashing equipment was considered not to have contributed to the loss of containers. However, the investigation found that the weights and distribution of containers in the affected bays were such that calculated forces exceeded allowable force limits as defined in the ship’s Cargo Securing Manual (CSM).
Dislodged containers six days after the accident
Source: ATSB
ATSB Chief Commissioner Greg Hood said the safe carriage of containers at sea depends on loading, stowing, and securing them in compliance with the ship’s CSM.
“Checking stowage plans for compliance with the Cargo Securing Manual requirements is increasingly achieved through loading computer systems. Notwithstanding the efficiency of computerised loading systems, the scale and pace of modern container ship operations puts significant pressure on ship’s officers to check and amend or approve proposed stowage plans at a late stage.”
Mr Hood noted that in that context, the planning process ashore offers the best opportunity to take all practical measures to ensure that the proposed stowage plan presented to ships officers complies with the CSM and is as safe as reasonably practicable.
The ATSB investigation found that the weights and distribution of containers in the affected bays were such that calculated forces exceeded allowable force limits as defined in the ship’s CSM. The investigation also identified that the stowage arrangement was not checked for compliance with the CSM’s calculated lashing force limitations during the cargo planning process ashore.
“This left sole responsibility for compliance with the ship’s officers, with limited options to resolve deficiencies at a late stage in the process without unduly impacting operations,” Mr Hood said.
Further, the officers did not use the ship’s loading computer system and its lashing calculation program to check if the stowage arrangement complied, as they probably did not have an adequate understanding of the system.
“Weather forecasting, routing and good navigational practices in adverse weather all play a part in minimising the risk of injuries to crew and damage to ship, cargo and environment,” Mr Hood said.
“However, safe and effective container stowage planning is the primary control measure in managing the risks involved in carrying containers by sea.”
As a result of this accident, the ship’s managers, Yang Ming, have taken a number of safety actions to address the identified issues. These include requiring checks of lashing forces during the initial cargo stowage planning stage ashore, providing regular training of shore planners in multiple aspects of cargo loading and securing, and training responsible ship’s officers in the use of the ship’s loading computer system.
“The ATSB considers that the safety actions taken by Yang Ming have adequately addressed the issues that our investigation identified,” Mr Hood said.
An ATSB investigation into a landing accident involving a Van’s RV-6A at William Creek, South Australia on 28 July 2019 found that the aircraft’s nosewheel landing gear’s strut or fork made contact with the runway, bending the nose gear under the aircraft.
The accident occurred when the aircraft was landing on an unsealed runway at William Creek. During the landing, the aircraft’s main gear touched down first, before the nose gear touched down momentarily. The pilot would later note that although the nose gear lifted off the runway, the main gear stayed on the runway.
When the nose gear made contact with the runway surface for the second time, it bent under the aircraft. The propeller then struck the runway and the aircraft skidded on its nose before flipping over coming to a rest inverted. The pilot sustained serious injuries and the passenger minor injuries, while the aircraft was substantially damaged.
Pilots of tricycle variants of Van’s aircraft need to take into account the many factors that can affect the ground clearance of their aircraft’s nose gear.
The ATSB investigation found that during the landing sequence the nose gear fork or strut made contact with the runway surface and bent underneath the aircraft. The investigation also established that the nose gear’s strut and fork had sustained no fractures, and that instead, the top of the strut had bent, near the engine mount.
“A reduction in the nose gear ground clearance during landing can result in the nose gear strut or fork impacting the runway and affect the structural integrity of the nose gear,” said ATSB Director Transport Safety Stuart Macleod.
“In the tricycle variants of Van’s aircraft, the factors that can affect nose gear ground clearance include the dynamics of the landing, tyre pressure, weight over the nose gear, and runway condition and characteristics.”
In 2007, Van’s issued a mandatory Service Bulletin with a redesigned nose gear that provided greater clearance. The aircraft that flipped at William Creek was compliant with this Service Bulletin and was also fitted with two after-market devices aimed at reducing the risk of a nose-gear collapse and aircraft inversion.
Corrosion in the carburettor of a Cessna 182’s engine, which led to a power loss after take-off and a subsequent forced landing, demonstrates the importance of following maintenance periodic inspection requirements.
On the morning of 6 January 2019, Cessna 182 registration VH-DGF took off from Tooradin Airfield, Victoria for skydiving operations with the pilot and four parachutists onboard. The aircraft continued to climb but at about 400 ft the engine sustained a sudden power loss. Climb performance was affected and the propeller windmilled.
The pilot lowered the aircraft nose and identified a suitable location for a forced landing. The aircraft touched down in a relatively flat and open paddock and initially bounced and passed through two boundary fences. The left wing strut then collided with a tree, folding the left wing over on top of the right wing. The Cessna then collided with a third fence, crossed a private road and collided with a fourth fence collapsing the nose landing gear where it come to a stop.
With limited time and height available, the pilot displayed sound airmanship and decision making.
The aircraft was substantially damaged, but there were no injuries to the pilot and passengers. However, the investigation report does note that by not wearing the available upper torso restraint the pilot exposed himself to significant unnecessary injury risk, and highlights that a substantial body of research shows that wearing an upper torso restraint significantly reduces the risk of injury compared to just wearing a lap belt only.
Following the accident, subsequent examination of the carburettor found a significant amount of aluminium oxide deposits in the carburettor float bowl and directly below the carburettor nozzle and main jet assembly.
Loose aluminium oxide deposits likely blocked fuel flow within the carburettor resulting in the engine losing power shortly after take-off.
With limited time and height available, the pilot displayed sound airmanship and decision-making by accepting the risk of a minor accident and conducting a forced landing rather than turning back and risking loss of control and the possibility of a much more serious outcome, the report notes.
This investigation also highlights the importance of following the maintenance program for your aircraft to ensure its serviceability, particularly as in this case, draining and flushing the carburettor at its periodic inspection.
The ATSB was unable to determine the extent to which this action was actually conducted during the six inspections since the engine and carburettor were overhauled in December 2011.
Ineffective execution of checklists and the absence of nose-wheel chocking contributed to an Avro RJ85 airliner rolling forward after engine start and colliding with aircraft stairs and a light pole at Perth Airport, a new ATSB report details.
During the 30 July 2019 occurrence, the flight crew of a Cobham Aviation Avro RJ85 were preparing their aircraft for departure for a charter flight with two cabin crew and 62 passengers on-board.
The subsequent ATSB investigation found that the flight crew did not effectively check the brake system pressure during two separate pre-flight checklists, which meant they did not detect that there was insufficient pressure within the braking system, and did not identify that the system needed to be pressurised prior to engine start. (The aircraft had been parked after its previous flight for a number of hours; longer than the brake accumulator reservoir could retain pressure.)
The ATSB found that the initial and primary missed checks related to the captain not performing checklist items as required, and the first officer not effectively monitoring the checking actions of the captain and not independently checking the pressure systems.
Because of the missed checklist items, on engine start there was no brake pressure in the aircraft’s parking brake system. Once the captain gave the ground engineer clearance to remove the main wheel landing gear chocks, there was no other restraint in place to prevent an inadvertent roll forward, as the operator’s procedures did not involve repositioning chocks on the nose-wheel of departing aircraft.
Once started, the combined thrust of the aircraft’s four engines at idle power and the slight apron slope caused the aircraft to inadvertently roll forward. The crew attempted to apply the aircraft brakes. However, because there was no brake pressure, these attempts were ineffective.
The normal after-start checks would have pressurised the brakes, however because the crew were responding to the unexpected roll-forward, they did not perform these checks. The ATSB found that the crew had a very limited opportunity to take corrective action to prevent the collision. The close proximity of the edge of the apron and the surprise associated with the unexpected roll-forward reduced the crew’s ability to respond before it collided with portable aircraft stairs. The aircraft then collided with a bollard in front of a light pole, and then the light pole itself.
“This investigation highlights the importance of ensuring all checklist items are addressed,” says ATSB Executive Director Transport Safety Nat Nagy.
“As highlighted in this accident, individuals can be vulnerable to omitting checklist items and this can lead to accidents.
“Aviation safety relies on a resilient safety system involving multiple defences. In the context of multi-crew operations, one of the key defences against this type of accident is the other pilot monitoring and cross-checking the pilot who is completing the checklist. This can provide a last line of defence to trap individual errors.”
Mr Nagy also noted that although safety systems should seek to reduce errors developing, where possible engineering defences, like wheel chocks, should also be used to reduce error consequences.
The report notes that Cobham have reiterated to their check and training captains the importance of vigilance during checklists, and that they were planning to update procedures to require the use of nose-wheel chocks when dispatching aircraft from stand-off bays.
After a loss of engine power, probably due to insufficient fuel or an in-flight fuel management error, a twin-engined Cessna 310 aircraft did not maintain a safe flying speed before it collided with terrain just short of the runway, an ATSB investigation has found.
The Cessna T310R was on approach to land at a private airfield at The Lakes, adjacent to the Pacific Highway south of Port Macquarie on the NSW North Coast, while conducting a private flight from Toowoomba, Queensland, with a pilot and passenger on board. When the aircraft was about 8 km from the runway, a witness recalled hearing what he thought was a single-engine aircraft ‘cough’ and then stop. A separate witness, who was driving south on the Pacific Highway, recalled seeing the aircraft descending slowly, then roll to the left, pitch down and descend rapidly to the ground.
The aircraft was subsequently found to have collided with terrain, coming to rest in a narrow-wooded strip of land between the highway and the main northern railway line, about 800 metres from the runway threshold. The pilot and the passenger were fatally injured, and the aircraft was destroyed in the accident.
The ATSB investigation identified that during the final descent, the aircraft’s left engine was not producing power and the right engine was operating at low or intermittent power. The loss of engine power was probably the result of either insufficient fuel for the flight or an in-flight fuel management error.
It is imperative that the pilot retains control of the aircraft and maintains a safe airspeed.
Despite that power loss, examination of the wreckage identified that the aircraft was configured for a powered approach, in a high‑drag configuration with the left and right engine propellers unfeathered, the landing gear down and the flaps partially extended. The low engine power combined with the high-drag configuration meant that the aircraft’s speed and altitude could not be maintained.
The investigation report notes that maintenance of a high‑drag configuration while the aircraft’s performance declined indicated that either the pilot did not recognise any engine abnormalities until late in the approach or assessed that sufficient engine power remained to reach the runway.
ATSB Chief Commissioner Greg Hood said this accident highlighted how a loss in power requires different responses depending on whether an aircraft has single or multiple engines.
“However, regardless of the configuration, in order to maximise the survivability outcome, it is imperative that the pilot retains control of the aircraft and maintains a safe airspeed,” Mr Hood said.
“Where the aircraft’s performance degrades to the point that continued safe flight is not possible, the pilot must shift their focus to conducting a forced landing.”
Mr Hood also stressed that pilots need to routinely follow recognised fuel management practices in order to maintain the highest level of safety and avoid fuel exhaustion or starvation events.