High rate of descent

An AW139 helicopter experienced an uncommanded high rate of descent during a search for a recreational fishing vessel while the crew was flying with the aid of night vision goggles in bushfire-affected low visibility conditions at night.

An ATSB investigation into the 13 May 2018 incident found the pilot, who was flying under night visual flight rules, lost visual cues while descending to 400 feet above ground level to confirm the potential source of a transmitting EPIRB beacon, in the vicinity of Salt Water Arm, approximately 40 km east of Darwin. The pilot’s intent was to decrease rate of descent and airspeed before activating the helicopter autopilot’s auto-hover (HOV) mode at 400 ft above ground level (AGL), however at the point of ‘HOV’ mode activation, the AW139 was descending at over 1,300 feet per minute.

The aircrew officer, who was also using night vision goggles and was monitoring the descent from the helicopter’s main cabin, alerted the pilot over the intercom of the high rate of descent, before calling ‘Climb! Climb! Climb!’

The crew’s use of standard patter and practiced drills allowed them to recover the situation and avert an accident.

By this point the pilot had clear visual cues and also detected the rapid rate of closure with the ground, and instituted a recovery in accordance with drilled emergency procedures, overriding aircraft automatics and using forward cyclic and collective to reverse the rate of descent.

The aircraft descended to a height of 31 feet AGL before attaining a positive rate of climb. Occupied with flying the recovery procedure – flying solely through the outside picture and the attitude indicator – the pilot did not observe a main transmission torque limit exceedance message.

The helicopter safely recovered to Darwin, and subsequently returned to the Salt Water Arm area on a second flight to conduct a successful search for the source of the EPRIB transmission, found to be a small recreational fishing boat.

Describing the effect of smoke on pilots, ATSB Director Transport Safety Stuart Macleod said “During the approach to hover in a degraded visual environment, searching outside for visual cues drew the pilot’s attention away from the flight instruments. This resulted in flight instruments not being referenced when they were needed.

“With the aircrew officer in the helicopter’s main cabin, in anticipation of having to operate the winch, rather than next to the pilot in the cockpit, this negated the benefit of having a trained and competent crewmember to assist the pilot, resulting in a degraded monitoring capability in the approach to hover.”

Application of good crew resource management and practiced recovery techniques supported the crew in restoring control, Mr Macleod noted.

“The crew’s use of standard patter and practiced drills allowed them to recover the situation and avert an accident.”

When on the ground at Darwin, the crew could not confirm indications of the main gearbox overtorque exceedance, and a maintenance message was not detected on the crew alert system, which displays messages regarding the operation and condition of the aircraft for crew information and action. As a result, the helicopter was flown on the second sortie that evening, despite the overtorque exceedance requiring the AW139 to be grounded until the engine and airframe manufacturers could assess the helicopter as serviceable.

In reference to the uncommanded high rate of descent, Mr Macleod said the incident underlines the need for pilots to be aware of the human factors hazards associated with a loss of visual references.

“Pilots can protect themselves by maintaining the use of instrument scans in approaches at night, and making use of monitoring by trained and available crewmembers,” he said. “Instrument flight rules (IFR) pilots in IFR-rated aircraft should prioritise the use of inadvertent instrument meteorological conditions drills and pre-planned exit routes over recovery of visual meteorological conditions.”

The investigation also highlighted that flight crew and engineering teams should not rely solely on indicators, or the absence of indicators, to determine airworthiness.

“If there is any reason to suspect that aircraft limits have been exceeded, operators should run diagnostics to determine the airworthiness of the aircraft beyond doubt,” Mr Macleod said.

Since the incident the helicopter’s operator, CareFlight, introduced three new risk controls to prevent a similar occurrence, including updating standard operating procedures with stabilised approach criteria to require an immediate go-around if the aircraft leaves a prescribed range of parameters, and improved auto hover functions advice. In addition, the ground-based training syllabus now incorporates controlled flight into terrain avoidance training.

The investigation also noted that the EPIRB was not registered to its current owner and was incorrectly placed in the boat, causing the beacon’s signal to be scattered and leading to a loss of accuracy in the helicopter’s direction-finding equipment. As a result, the mission’s complexity and time taken to rescue were increased.

Read the final report: Loss of control in flight involving Leonardo Helicopters AW139, VH-YHF, near Adelaide River mouth, 38 km east-north-east of Darwin, Northern Territory, on 13 May 2018


Track obstruction risks

A passenger train sustained minor damage after colliding with a metal awning from a modified shipping container that was being transported by a freight train, which had opened in transit before striking a bridge and falling onto the track.

The 20 foot container, modified with a large side opening awning for use as a canteen, was travelling on Pacific National train 7WB3 from Newcastle to Brisbane on 17 June 2018. As the container passed over Wilson River Bridge, near Telegraph Point in NSW, the open awning struck the bridge superstructure and fell onto the track.

The ATSB investigation into the incident established that the awning had opened twice previously during transit. On both those occasions the crew re-secured the awning, but they were unaware of the third opening before the awning struck the bridge.

Train 7WB3 then continued north and stopped in the Telegraph Point passing loop to allow southbound passenger train NT32 to pass on the mainline. As NT32 crossed south over the Wilson River Bridge, it struck the awning and sustained minor damage to brake equipment on the train’s leading bogie.

The ATSB found that the awning was only held closed by spring-loaded bolts accessed from the inside of the container. This was not compliant with Pacific National’s Freight Loading Manual (FLM), which required a system that could be locked and was externally visible to assure that openings remained secure and enable examination by inspection staff. Further, inspections conducted by Pacific National terminal operators at the departure location did not identify the modified container or the absence of locks.

Any item on a container that can open into the rail corridor represents a potential risk as, should they come open, they may strike infrastructure, opposing trains or bystanders.

“The absence of externally visible locks meant there was no way of knowing whether the modified container’s awning was adequately secured,” ATSB Transport Safety Director Dr Stuart Godley said.

“Should any opening come open during operation, they may strike infrastructure, opposing trains or bystanders.”

The ATSB also noted that, while Pacific National made the FLM available to customers, they did not actively advise them when they had a responsibility identified by the manual and did not have a process for ensuring customers complied with the manual’s requirements. Therefore, in this case, the customer did not notify Pacific National that the container was modified as they were not aware of a requirement to do so. Additionally, the training and checking processes for terminal operators who carried out inspections did not include the FLM requirements for modified containers. This removed an opportunity for the requirements to be reinforced and practiced during training and regular checking of inspection staff.

“This incident highlights the importance of having processes in place to advise customers of the requirements for the safe transport of modified containers and to ensure compliance,” Dr Godley said

Since the incident, Pacific National has implemented a range of processes to ensure customers are aware of, and are compliant with their FLM requirements. This has included the development of an online course and an auditing program to monitor compliance and performance.

In addition, Pacific National have also introduced a number of training and checking measures for inspection staff.

Read the final report: Track obstruction due to loss of freight from train 7WB3 and subsequent impact of passenger train NT32 with track obstruction, near Telegraph Point, New South Wales, on 17 June 2018

Landing gear wheel failure

After a wheel on one of its Boeing 737s failed, Virgin Australia implemented new landing gear wheel inspection requirements, while the wheel manufacturer, Safran, updated the relevant component maintenance manual.

The wheel failure event occurred on 4 January 2017 when the 737-800 was holding on taxiway Brisbane Airport B3 when the crew heard a loud noise they thought was a burst tyre. The crew attempted to taxi back to the gate, but were held short when an engineer observed that the left main landing gear main wheel assembly had failed.

The flight was cancelled and passengers disembarked, however the aircraft could not be jacked and towed via the axle due to the damaged wheel. Instead, wing jacks were used to allow a double wheel change on the tarmac. The aircraft was then towed to a maintenance facility for examination.

…There were no mandated inspections suitable for detecting such loosening.

An ATSB investigation found that the wheel had ruptured due to tie bolt assemblies having loosened while in service. This allowed the two wheel halves to move relative to each other, resulting in a fatigue crack and eventual wheel rupture. The loosening was most likely due to the presence of anti-seize compound between the wheel halves, which affected the clamping forces.    

“This incident highlights the importance of compliance with all aspects of manufacturers’ maintenance procedures, including the appropriate application of anti‑seize,” said ATSB Director Transport Safety Stuart Macleod. “This is especially important if, as in this case, there is no simple means of detecting the effect that such excess product can have on fastener security.”

The ATSB found that while the bolt assemblies on this single-web wheel-type were more prone to in-service loosening than dual-web wheels, there were no mandated inspections suitable for detecting such loosening. There were also no mandated risk controls to prevent loosening or subsequent rupture.

Virgin has advised that in response to this incident, it has implemented regular inspections to identify and prevent the loosening of tie bolt assemblies. Safran, the wheel manufacturer, updated the wheel’s component maintenance manual with more detailed instructions for applying anti-seize compound.

Finally, Boeing advised 737 NG operators of two possible courses of action to address the issue of potential wheel failures based on two optional service bulletins that it had in place prior to the occurrence.

The particular wheel type was installed on approximately 2,000 737 NG aircraft in service worldwide. Boeing has delivered approximately 7,000 737 NG aircraft in total.

Read the final report: Main landing gear wheel failure during taxi involving Boeing 737, VH-VUH, at Brisbane Airport, Queensland, on 4 January 2017

Accident highlights hypoxia risk

The pilot of a Cessna Grand Caravan was almost certainly incapacitated, possibly from hypoxia, when his aircraft flew uncontrolled into the ocean off the east coast of Japan.   

The Australian-registered Cessna 208B (VH-FAY) was being ferried from Perth to Mississippi in the United States via the Northern Pacific when on the morning of 27 September 2018 it departed from Saipan Airport in the Northern Mariana Islands bound for New Chitose Airport in Hokkaido, Japan.

After climbing for about an hour, the aircraft levelled off at 22,000 feet, while after 2 hours and 20 minutes into the flight, the pilot contacted Tokyo Radio flight information service on HF radio to make a mandatory position report. The aircraft was next due to report about an hour and 20 minutes later, when overhead the SAGOP reporting point, but no contact with Tokyo Radio was made. Tokyo Radio subsequently made repeated attempts to communicate with the pilot, without success.

About 4.5 hours after the pilot’s last communication, two Japan Air Self-Defense Force (JASDF) aircraft intercepted the Cessna. The pilot did not respond to the intercept in accordance with international intercept protocols, either by rocking the aircraft wings or turning, and the aircraft continued to track at 22,000 feet on its planned flight route. The JASDF pilots were unable to see into the cockpit to determine whether the pilot was in his seat or whether there was any indication that he was incapacitated.

After about 30 minutes, the JASDF pilots observed the aircraft descend into cloud. The aircraft descended rapidly and disappeared from radar less than 2 minutes later. Within 2 hours, search and rescue personnel located the aircraft’s rear passenger door. No other aircraft parts were located and the pilot was not found.

Rear passenger door

Figure 3: Rear passenger door.
Source: Aircraft operator

Source: Aircraft operator

The ATSB’s subsequent investigation found that while the aircraft was in the cruise on autopilot, the pilot almost certainly became incapacitated. Consequently, about 5 hours after the last position report, without pilot intervention to change fuel tanks, the aircraft’s engine stopped, likely due to fuel starvation. This resulted in the aircraft entering an uncontrolled descent into the ocean.

The effects of hypoxia can be insidious.

Director Transport Safety Stuart Macleod said that while the cause of the incapacitation could not be determined, and a medical event could not be ruled out, the pilot was operating alone in an unpressurised aircraft at 22,000 feet and probably using an unsuitable oxygen system, which increased the risk of experiencing hypoxia.

“Operating unpressurised aircraft above 10,000 feet requires careful oxygen management and planning,” Mr Macleod said.

“Where an increased risk of hypoxia exists, good risk management practices should be used for flight planning. Because the effects of hypoxia can be insidious, training in recognition of early symptoms of hypoxia can increase the time available to react, descend and resolve any issues.”

As a result of this accident, the aircraft operator amended its operation manual to include additional guidance for international ferry flights. It also created an oxygen-use guide and a specific risk assessment for positioning (ferry) flights.

Read the report: Collision with water involving Cessna 208B, VH-FAY, 185 km north-east of Tokyo, Japan, on 27 September 2018

Bogie fatigue cracking

A fatigue crack in a coal train wagon bogie went undetected during preventative maintenance before it escalated to a full fracture, increasing the risk of derailment, an ATSB investigation has highlighted.

On 12 December 2017 Pacific National coal train TM78A was undergoing a roll-by inspection at Kooragang Coal  Terminal in Kooragang, New South Wales, when a maintenance worker identified a fracture on the lead bogie of the train’s 35th wagon. The train was stopped and the wagon was removed for inspection.

An investigation into the cracking, conducted on behalf of the ATSB by NSW’s Office of Transport Safety Investigation (OTSI), found that the fatigue crack had gone undetected during earlier preventative maintenance, and that it was probable that the fracture was visible the day before during unloading of the wagon, but had gone undetected.

Identifying this fracture in time likely prevented a derailment.

The NDCA bogie frame design has a history of fatigue cracking, which increases the risk of derailment if the cracking is not identified. Pacific National had processes in place to identify fatigue cracking, but this crack was likely not detected due to the location of the defect on the bogie frame.

OTSI COO and Deputy Chief Investigator Kevin Kitchen said the incident highlights how asset managers should ensure that inspection techniques effectively monitor and report on the condition of assets.

“Risk controls should also be continuously assessed to control risk to an acceptable level through the life cycle of an asset,” Mr Kitchen said.

In response to the incident, Pacific National has made changes to the maintenance standard used during scheduled maintenance, increasing the area of the bogie frame subjected to non-destructive testing. This change is aimed at identifying and addressing fatigue cracking prior to any escalation of defects.

“Identifying this fracture in time likely prevented a derailment,” Mr Kitchen said. “However, if the worker who identified the defect had been positioned on the opposite side of the train, it could have been missed.”

Read the final report: Fractured bogie frame on coal train TM78A, at Kooragang, New South Wales, on 12 December 2017

Fatigue crack engine failure

A fatigue crack in a turbine blade spread rapidly, causing a helicopter’s engine failure, an ATSB investigation found.   

The incident occurred when a twin-engined Airbus Helicopters AS355F-1 helicopter, registered VH-SEV, was completing an air-taxi from a hangar to a maintenance facility at Sydney’s Bankstown Airport. On board were the pilot and one passenger.

As the skids touched the ground on landing, the pilot heard a loud ‘squeal’ from the helicopter’s right-hand side. The pilot scanned the instrument panel and observed the engine gas generator speed (Ng) drop to 55 per cent and the right-hand engine chip light illuminate. A few seconds later, the pilot observed smoke coming from that side of the aircraft and immediately shut down the right-hand engine.

Mechanics from a nearby workshop quickly extinguished the engine fire. There was substantial damage to the engine, and minor heat damage to the surrounding structure of the helicopter.

Any pilot, regardless of their level of experience, can find themselves confronted with an unexpected failure.

“Any pilot, regardless of their level of experience, can find themselves confronted with an unexpected failure,” said ATSB Director Transport Safety Stuart Macleod. “The pilot’s quick response to the unexpected failure helped ensure the best possible safety outcome.”

The ATSB investigation found that single third-stage turbine wheel blade failed due to fatigue cracking, resulting in secondary damage to the engine, and total engine failure.

“This incident reinforces that it is important for pilots to monitor aircraft performance parameters continuously for abnormal indications,” said Mr Macleod.

Engine manufacturer Rolls-Royce advised the ATSB that, with the Rolls-Royce 250 enhanced power turbine engine, a dwell of just a few seconds can be enough to initiate damage and propagate a crack to failure.

In response, Rolls-Royce is redesigning the third-stage turbine wheel to improve its tolerance to fatigue cracking and operation at responsive wheel modes.

The report AO-2018-021, provides important advice for operators of aircraft with Rolls-Royce 250 enhanced power turbine engines.

Read the final report: Engine failure involving an Airbus Helicopters AS355F-1, VH-SEV, Bankstown Airport, New South Wales, on 12 March 2018

Sling load accident

The ATSB is highlighting the precautions necessary for sling load operations after a load unexpectedly fell from a Bell 205 helicopter, striking and seriously injuring a worker on the ground.

The helicopter, registration VH-HUE, was being used for external sling loading operations to move equipment from a staging area near Tantangara Dam to a drilling site about 3 km away, south-east of Talbingo, New South Wales, on 10 January 2019. As the helicopter approached the drop-off site, the load, comprising drill rod racks weighing about 1,200 kg, unexpectedly disconnected from the cargo hook. The falling load struck and seriously injured a loadmaster assisting on the ground.

In the course of investigating the incident, the ATSB examined the slings, shackle and hook, but could not determine the reason for the load being released from the hook. However, the ATSB found that the ground personnel had not been maintaining a safe distance from the load.

This incident highlights the dangers associated with external sling load operations.

“This incident highlights the dangers associated with external sling load operations,” ATSB Director Transport Safety Stuart Macleod said. “Unexpected events can occur, and ground personnel should take care to ensure they maintain their separation from external slung loads that are above head height.”

In this accident, the positioning of the ground personnel, in combination with the significant movement of the load as it contacted the ground, meant that they were exposed to higher risk.

“Each sling load operation can be unique, with different locations, different load shape, and different environmental conditions combining to create different safety considerations,” Mr Macleod said. “As a consequence, clear written procedures and detailed discussions prior to commencement of each operation are essential to ensure that all participants are aware of the unique dangers of the operation.”

Read the report: External sling loading accident involving Bell 205, VH-HUE, 39 km south east of Talbingo, New South Wales, on 10 January 2019

Floatplane and boat collision

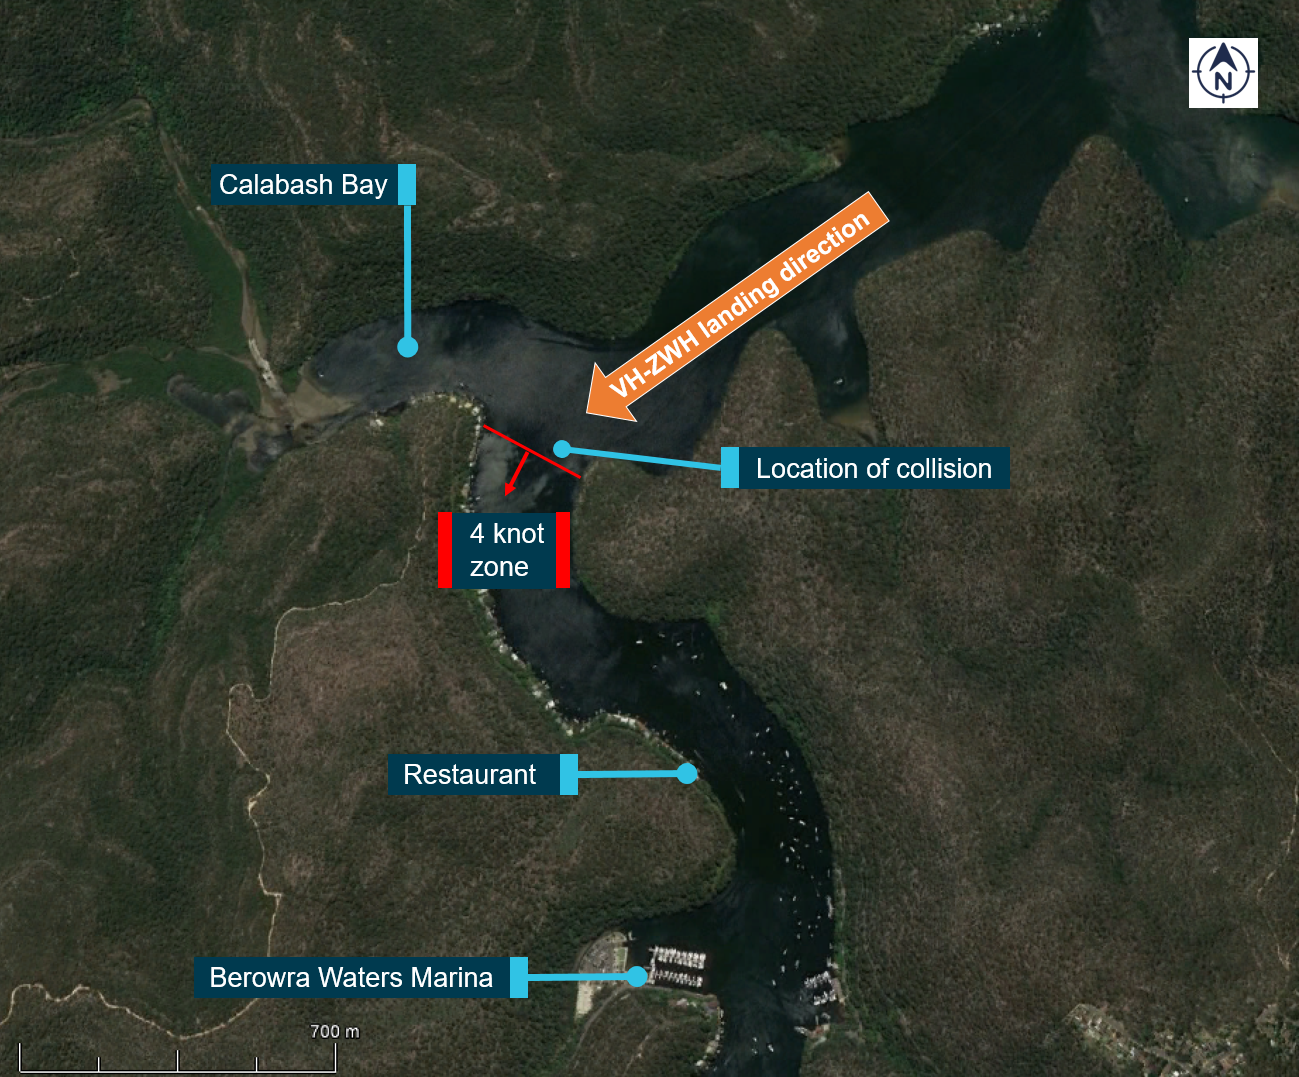
A collision between a Cessna Caravan floatplane and a small aluminium boat highlights the importance of scanning and assessing landing areas for potential hazards during amphibious flying.

The floatplane had just completed a water landing at Berowra Creek, in the Hawkesbury River catchment north of Sydney, on 29 June 2019.  After slowing down to taxi speed, the aircraft’s front left float bumped into a small stationary boat. There was no damage to the aircraft or boat, while one person in the boat sustained minor injuries.

The ATSB’s investigation into the incident found that the pilot did not see the boat due to a combination of factors including the weather conditions on the day as well as the colour, size, lack of movement and location of the boat as it was positioned in the aircraft’s direct path.

This incident highlights the importance of scanning and assessing landing areas for any potential hazards, and of the joint responsibility of both aircraft and marine vessels to see and avoid other aircraft and vessels operating on the water.

“This incident highlights the importance of scanning and assessing landing areas for any potential hazards, and of the joint responsibility of both aircraft and marine vessels to see and avoid other aircraft and vessels operating on the water,” said ATSB Director Transport Safety Dr Stuart Godley.

 “When choosing an operating speed for any vessel or aircraft on the water, consideration should be given to any potential blind spots and areas where other vessels could emerge.”

Subsequent to the incident the aircraft operator has advised its pilots to remain on the right hand side of the waterway to reduce the risk of a blind spot near the area of the incident.

In addition, as a standard operation, company pilots are to reduce the speed of the aircraft to an idle power taxi speed after landing, 100 m before the start of the 4-knot zone at Berowra.  

Read the final report: Collision with vessel involving Cessna 208, VH-ZWH, Berowra Waters, New South Wales, on 29 June 2019

Buffer stop collision

ro2019006_bufferstop.jpg

Source: ONRSR

The slow-speed collision of an empty passenger train into a buffer stop on 25 February 2019 highlights the importance of train safety systems to protect against driver error and incapacitation, an ATSB investigation notes.

After its passengers had disembarked, Metro Trains Melbourne train TD 6591 departed Newport Station for a siding where it was to be stabled (parked and secured). As the train approached the stabling location, the brakes were not applied in sufficient time to stop the train and it collided with the buffer stop.

The collision resulted in substantial damage to the front of the train and the buffer stop, and the driver was hospitalised with minor injuries.

In subsequent interviews the driver reported losing consciousness for a period of time prior to the collision, recalling entering the siding but having no other recollections until after impact. A subsequent medical examination found the driver may have fainted due to dehydration and lack of nutrition.

Analysis of data from the driver cabin’s Vigilance Control Event Recorder System (VICERS) showed that a brake application consistent with emergency braking was made about 1.5 seconds before impact, but that was after passing the required stopping point.

Train safety systems are an important protection against driver error and incapacitation.

“The driver may have been incapacitated immediately prior to the accident and therefore temporarily lost awareness, leading to the train not stopping at the designated stopping point as the driver did not apply the brakes in sufficient time,” said ATSB Director Transport Safety Dr Stuart Godley.

“However, due to limited and conflicting evidence the cause, duration and presence of incapacitation could not be determined.”

While the train was equipped with a safety system, comprising a pilot valve as part of the master controller, that was designed to apply the brakes in situations such as driver incapacitation, it did not activate in this incident. The recorded data indicated that sufficient pressure was maintained on the master controller, and therefore the only aspect of the train safety system that could have activated and applied the brakes to protect against driver incapacitation was not triggered.

Post-accident testing of the train’s braking system and the master controller hand pilot valve found no faults that would have contributed to a failure to stop.

“Train safety systems are an important protection against driver error and incapacitation,” Dr Godley noted.

“In addition, drivers are reminded to maintain their health and fitness for work to reduce the likelihood of incapacitation including maintaining adequate levels of nutrition and hydration as well as consideration of the potential impact of fatigue,” Dr Godley said.

Information on fatigue is available on the ATSB website.

Read the final report: Collision of passenger train TD 6591 with buffer stop, Newport siding, Victoria, on 25 February 2019

Flap and landing gear overspeed

Incorrectly calculated take-off speeds contributed to an Airbus A320 experiencing flap and landing gear retraction overspeed events, an ATSB investigation has established.

While preparing for a flight from Sydney to Melbourne, the flight crew of the Jetstar Airways A320 were unable to use two electronic flight bags to calculate and check take-off performance data, and instead used manual take-off charts.

But the flight crew inadvertently calculated speeds that were higher than required for the actual aircraft weight and environmental conditions, and those incorrect take-off speeds were not identified by independent verification and cross-checking.

Consequently, the aircraft did not rotate to the correct pitch attitude during its take-off roll, resulting in a higher acceleration rate than anticipated. As a result, the aircraft’s speed at rotation was only 16 knots below the maximum flap extended speed.

Following rotation, the pitch rate remained under the recommended rate, and continued to reduce with the aircraft’s speed increasing. The pilot flying was not alerted to the incorrect pitch attitude rotation; however the pilot monitoring called ‘speed, speed’ to assist in the management of airspeed. The flap extended limit speed was exceeded five seconds after rotation. 

This incident highlights the importance of independent validation and crosscheck of flight performance data, in particular performance speeds and aircraft weight.

When alerted to the impending overspeed, the pilot flying reduced the engine power in response, rather than increasing the aircraft pitch. The action of reducing the engine power was taken when the aircraft was below the safe altitude above ground.

Then, climbing through 2,800 feet, the flight crew reported hearing a buffeting noise, and they soon determined that the landing gear was still extended. The pilot flying immediately called ‘gear up’ and the pilot monitoring quickly retracted the landing gear without looking at the speed indication, which was 30 knots above the maximum landing gear retraction speed.

The flight crew discussed the occurrence and with no known adverse indications, they continued the flight to Melbourne without further incident.

“This incident highlights the importance of independent validation and cross-check of flight performance data, in particular performance speeds and aircraft weight,” ATSB Transport Safety Director Dr Stuart Godley said.

The ATSB found that when using the manual take-off charts, the procedure for the calculation for the correct take-off performance speed for the aircraft’s actual total take-off weight was not completed, resulting in a calculated rotation speed based on an aircraft weight significantly heavier than their actual take-off weight.

“This error was not detected through an independent validation crosscheck,” Dr Godley said.  

“This investigation emphasises the importance of considering reasonability and accuracy checks, consulting company procedures manuals in the event of electronic flight bag issues, and conducting a normal rotation followed by reference to the Speed Reference System,” Dr Godley said.

Read the report: Incorrect configuration involving Airbus A320, VH-VFX, Sydney Airport, New South Wales, on 29 September 2018