Site protection failings

ro2017009_news_1.jpg

On the morning of 31 July 2017, a team of four Sydney Trains infrastructure maintainers was conducting a series of regular inspection and measurements at points along the Illawarra Main and Local lines at Tempe in Sydney’s inner west.

Two of the workers were acting as an inspection team, entering the danger zone (the area within three metres horizontally from the nearest rail) and accessing the track.

The other two workers acted as lookouts, using the Lookout Working method, which consists of rules for working in the danger zone using lookouts, and requires all workers and equipment to be completely within a safe place a minimum of 10 seconds before rail traffic passes their location.

Conducting work on or near railway track can be dangerous if safeworking rules and procedures have not been correctly implemented.

At approximately 10.00am, an empty passenger train was travelling on the Illawarra Local line when the driver observed the work group in the danger zone. He applied the brakes and blew the horn, and the workers began to move off the line towards a safe place to the side of the track. A review of the CCTV footage from the train showed that the workers had not yet reached a safe place when the train passed their location, approximately seven seconds after the train first observed them. There were no injuries or damage.

The investigation, conducted on behalf of the ATSB by NSW’s Office of Transport Safety Investigations (OTSI), found issues with the workgroup’s reliance on Lookout Working for worksite protection. Each lookout had been positioned to watch in different directions – one monitoring for Up trains, the other for Down trains. This incident occurred when the Down lookout had turned away to monitor the situation with an approaching Up train (which did not pose an immediate risk to the work group), and then turned back to find that a Down train was also approaching. He was not able to sound the warning to the work group and give them sufficient time to clear the danger zone to a safe location before the train neared their location.

Compared to other worksite protection methods, Lookout Working does not warn, or restrict trains from approaching, or entering a work location. The investigation found that Lookout Working had been implemented in an area deemed not suitable on the Sydney Trains rail network.

Additionally, there was not a clear understanding within the work group of various elements of the Lookout Working system, resulting in reassessments not being made, the Up lookout being posted in an inappropriate area, and a misunderstanding of what constituted a safe place.

The ATSB safety message from this investigation stresses that where practical, rail transport operators must require track workers to continually re-assess the site risks, add and or combine safety measures (like an Automatic Track Warning System, or audible warning devices), or implement a higher form of protection.

Read the final report: Safeworking irregularity involving Lookout Working, near Tempe, New South Wales, on 31 July 2017

In-flight balloon fire

A hot air balloon in-flight fire demonstrates the importance of pilots preparing for the possibility of fire, including rehearsing emergency procedures and wearing appropriate protective clothing, a new ATSB investigation highlights.

ao2019001_news.jpg

The 26 December 2018 scenic flight had departed Wandin, Victoria, with a pilot and 15 passengers on board.

Twenty minutes into the flight, while at an altitude of about 800 ft, the pilot heard a small explosion from the front left burner and then observed a small fire had started on the outside of the burner. Despite attempts to extinguish the fire, it re-ignited twice and the pilot’s compartment caught fire.

About eight minutes after the fire first ignited, the pilot identified a suitable landing position. During the decent, the basket struck some treetops and ropes became tangled in the branches. The branches whipped around and into the basket, and one passenger sustained cuts to his hand.

As the basket touched the ground, the passengers on the right-hand side of the basket jumped out, causing the right side of the basket to lift off the ground again. In response, the pilot quickly pulled the red line to evacuate the hot air from the envelope and brought the basket back down to the ground. The remaining passengers then jumped out and ran to safety.

The fire continued to burn as the pilot secured the balloon. When emergency services arrived on site, flames had engulfed the balloon. By the time firefighters extinguished the flames, the fire had destroyed the balloon.

In the event of an in-flight balloon fire, the first priority must be the isolation of the fuel supply at the fuel tank.

The ATSB investigation found that a fuel leak at the front left burner has resulted in the fire. After the fire broke out, the hand-wheel valve on the liquid outlet of the fuel tank and the pilot burners were not shut off, which resulted in the pilot being unable to control the fire.

“Pilots experience a high workload during in-flight emergencies. However, in the event of an in‑flight balloon fire, the first priority must be isolation of the fuel supply at the fuel tank,” said ATSB Executive Director Transport Safety Mr Nat Nagy.

“In addition, it is good practice to rehearse emergency procedures by standing in the basket to run through the checklist steps.”

Mr Nagy noted that further ways to reduce risk to individuals and improve survivability outcomes include wearing appropriate protective clothing, including cotton long‑sleeved shirts and trousers, leather gloves, and enclosed footwear.

“Operators should also consider utilising componentry that provides a visual indication of the system status, for example, 90‑degree valves on liquid outlets.”

Read the final report: In-flight fire involving Kavanagh B-350 hot air balloon, VH-ZYO, near Coldstream, Victoria, on 26 December 2018

Passive level crossing accident demonstrates how sighting from road vehicles can be severly restricted

Sighting from road vehicles can be severely restricted at passively protected level crossings with an acute angle road-to-track interface, a new investigation highlights.

ro2016009_news.jpg

On 13 July 2016, a Warrnambool-bound passenger train collided with a semi-trailer at the Phalps Road level crossing at Larpent, near Colac, Victoria. The level crossing was passively controlled with stop signs.

When the truck initially stopped at the crossing, the train was more than 300 m away. The truck commenced moving towards the track when the train was between 220 and 260 m from the crossing. Unaware of the train approaching beyond his line of sight, the truck driver entered the level crossing.

The driver heard the train’s horn shortly before the locomotive struck the truck’s semi-trailer. After impact, the train’s locomotive and all passenger cars derailed. The locomotive driver, train conductor, 18 passengers and the truck driver were injured. There were no fatalities. 

… sighting from road vehicles can be severely restricted at passively protected crossings with an acute angle road-to-track interface. It is important that available risk controls be deployed in these circumstances and road users take special care…

The investigation, conducted by Victoria's Chief Investigator, Transport Safety, on behalf of the ATSB, found the driver was unable to detect the approaching train on his left due to his restricted view from the level crossing’s acute road-to-rail angle and the composition of the truck’s passenger-side window.

The ATSB safety message from this investigation highlights that sighting from road vehicles can be severely restricted at passively protected crossings with an acute angle road-to-track interface. It is important that available risk controls be deployed in these circumstances and road users take special care.

The ability of a truck driver to see along a railway track to their left can be affected by in-cab obstructions. The Australian Design Standard for passively controlled level crossings accounts for this possibility by requiring a viewing angle of no more 110 degrees for a driver looking to their left from the straight-ahead direction. If this viewing angel is exceeded, passive level crossing controls should not be used.

The investigation found that for a vehicle stopped at the northern side of the Phalps Road level crossing, the viewing angle to achieve the required sighting distance was 116 degrees. The Phalps Road level crossing was subsequently upgraded to active protection controls in August 2016.

Since the accident, V/Line has taken action at 25 passenger line passively controlled level crossings with left-hand viewing angles that exceed the Australian Standard. Nine have been upgraded, one has had restricted access gates installed and 15 have had speed restrictions put in place. A further 24 crossings have also been nominated for upgrade.

Read the final report: Level crossing collision between truck and passenger train 8753, Phalps Road, Larpent, Victoria, on 13 July 2016

Compressive rail stress risk

The derailment of a loaded coal train between Emerald and Rockhampton in Queensland in January 2018 highlights the need for track managers to develop, maintain and consult network hazard registers to identify locations at risk of buckling due to compressive rail stress, according to a new ATSB investigation.

ro2018005_news.jpg

The day before the derailment, the affected track had been subject to ballast-cleaning operations. The track was then tamped, aligned, and stabilised, with a second and final pass of this work taking place the next morning.

That afternoon, as the nearly 2 km long train EF01 was descending a steep grade, the driver noticed a track buckle forming ahead of the train. After applying emergency braking the train came to a halt 65 seconds after the lead locomotive had passed over the track buckle.

The first wagon to derail travelled for over half a kilometre before the train stopped. Of the 17 wagons that derailed, 13 were extensively damaged and unlikely to be repaired. Just over half a kilometre of track on the down line and 54 m of track on the adjacent up line was damaged, with rails, sleepers and overhead line equipment needing replacement.

This investigation highlight the importance of developing, maintaining and consulting a network hazard register to identify locations at risk of buckling, and producing site-specific risk assessments that consider rail stress when planning track disturbing maintenance work.

The ATSB determined the accumulative effect of the track’s steep grade, with its proximity to a turnout and a high ambient temperature lead to the track to buckle. The ATSB also found the ballast cleaning operational plan did not consider compressive rail stress as a risk at this location.

”This investigation highlights the importance of developing, maintaining and consulting a network hazard register to identify locations at risk of buckling, and producing site-specific risk assessments that consider rail stress when planning track disturbing maintenance work,” said ATSB Director Transport Safety Dr Stuart Godley

“The accident also demonstrates that effective rail stress management is dependent on a knowledge of the rail stress free temperature and the identification of any variations from that stress free temperature.”

As a result of the accident, track manager Aurizon Network has changed its procedures to ensure a temporary speed restriction is applied to all work sites on which ballast undercutting has been performed. The restriction is to remain in place until rail adjustment or stress testing has been completed and it has been determined that the rail stresses are within accepted limits.

In addition, sites with a high risk of compressive rail stress will be identified and added to the site hazard map before conducting ballast cleaning.

Read the final report: Derailment of coal train EF01, Duaringa, Queensland, on 24 January 2018

Powerline hazards during spraying

A Robinson R44 helicopter striking a powerline while conducting aerial spraying provides another example of the dangers posed by powerlines during low-level operations, an ATSB investigation has highlighted.

The R44 was spraying weeds at Bool Lagoon, near Naracoorte, South Australia on 13 March 2019. Before the incident flight, the pilot had passed successfully under a powerline, which spanned a drainage channel to the west of Bool Lagoon, on three occasions during that days’ spraying operations.

The pilot then started a spray run from the eastern end of the drainage channel, and flew west towards a weir bridge and the powerline, which the pilot was aware of the presence of. Just before the bridge, the pilot noticed the helicopter was slightly lower than intended to provide adequate clearance over the bridge. The pilot positioned the helicopter to pass over the bridge and then under the powerline.

The ATSB found the pilot lost awareness of the position of the powerline as he manoeuvred over the bridge, and nearby vegetation likely reduced the ability of the pilot to regain that awareness.

This accident provides another reminder of the dangers posed by powerlines during low-level spraying operations.

The powerline struck the centre of the helicopter’s front section just above its headlights and cut into the helicopter cabin and control instruments. The helicopter landed hard on the bank of the drain and was destroyed. The pilot escaped with minor injuries, and there was no post-impact fire. The helicopter had been fitted with a bladder-type fuel tank, and there was no indication of a fuel leak. The bladder-type fuel tank probably reduced the likelihood of a fuel leak and post-impact fire following the collision.

“This accident provides another reminder of the dangers posed by powerlines during low-level spraying operations,” said ATSB Director Transport Safety Dr Stuart Godley.

“As this accident highlights, there may be limits to the extent to which operators can mitigate the risk of wirestrike during repeated low-level operations near powerlines.”

The ATSB points pilots and operators to a booklet jointly produced with the Aerial Application Association of Australia (AAAA), 

, which contains numerous lessons learnt from wirestrike accidents for pilots and operators. The AAAA also recently launched their Powerline Safety Program(Opens in a new tab/window) which promotes the marking of powerlines by powerline network operators wherever it is requested by a pilot, aviation company or landholder.   

“Pilots and operators involved in low-level aerial spraying are also reminded that flight helmets are vital to reducing the risk of injury in the event of an accident,” Dr Godley said.

Read the final report: Wirestrike involving a Robinson R44, VH-ZWK, 20 km from Naracoorte, South Australia, on 13 March 2019

ECDIS navigation risk

The ATSB investigation of the grounding of the Australian Border Force Cutter (ABFC) Roebuck Bay on Henry Reef has revealed underlying safety issues with the effectiveness of ECDIS type-specific training, ECDIS software updates and the use of a single point feature to represent relatively large physical features on electronic navigational charts.

mo2017009_final_figure-7.jpg

While planning the passage from Saibai Island in the Torres Strait Islands archipelago to Lizard Island, south-east of Cape Melville, ABFC Roebuck Bay’s previously used passage plan was amended, with its route inadvertently plotted over Henry Reef. 

The ship’s electronic chart display and information system (ECDIS) identified the reef as a danger to the planned route, however, the crew did not identify the danger either visually or by using ECDIS. The vessel continued on the amended route and grounded on Henry Reef just after midnight. There were no reported injuries or oil pollution, but the vessel sustained substantial damage.

The ATSB found the crew’s ability to check the amended route was limited as their training was not effective in preparing them for the operational use of their on board ECDIS.

The ATSB‘s investigation highlights that the safe and effective use of ECDIS as the primary means of navigation depends on operators being thoroughly familiar with the operation, functionality, capabilities and limitations of the specific equipment in use on board their vessel.

“ECDIS type-specific training needs to be designed, delivered and undertaken so operators have the required knowledge to confidently operate ECDIS as intended by the manufacturer,” ATSB Chief Commissioner, Greg Hood said.  

The ATSB also found the vessel’s ECDIS was not updated to the latest International Hydrographic Organization (IHO) standards and lacked the enhanced safety features of a new presentation library of symbology.

The ATSB reminds regulators, manufacturers, hydrographic offices and other concerned parties that their ultimate goal must be to eliminate the significant risks with the use of ECDIS or at least reduce them to an acceptable level in terms of navigational safety.

“Like all on-board equipment, ECDIS needs to be maintained and compatible with the latest applicable standards,” Mr Hood said.  

 “With the recent introduction of ECDIS as the sole means of marine navigation and the replacement of paper charts, the grounding was an opportunity for the ATSB to explore any potential safety impact of ECDIS in a real-world operational environment.”

The investigation involved interviews with Australian Border Force officers, crew and shore staff and hydrographers from the Australian Hydrographic Service and the ECDIS manufacturer. Extensive ECDIS analysis was also carried out, as was various ECDIS simulations and testing.

“As a result of the investigation, the ATSB considers the use of point features in electronic navigational charts to represent areas of relatively significant size on the earth’s surface is likely to increase the risk of the hazard posed by such features being misinterpreted and potentially reduce the effectiveness of ECDIS safety checking functions,” Mr Hood said.

 “While this did not specifically contribute to the grounding of Roebuck Bay, the investigation has shown that the implementation of ECDIS has introduced some unintended risks to marine navigation.”

The ATSB recognises that ECDIS and electronic navigational charts are an essential tool for navigation with many safety benefits; however, operating crew need to be aware that navigating with ECDIS is fundamentally different from navigation with paper charts.

“By allowing operators to view and change an electronic navigational chart to a larger compilation scale, ECDIS can make single point features representing rocks, wrecks and other obstructions appear progressively smaller as the scale is changed, creating the impression it is clear of a ship’s route or further away than what it actually is,” Mr Hood said.

ECDIS is a complex software-based system and the ATSB acknowledges the many challenges faced in its design, manufacture, and operation to ensure navigational safety.

“The ATSB safety message from this investigation reminds regulators, manufacturers, hydrographic offices and other concerned parties that their ultimate goal must be to eliminate the significant risks with the use of ECDIS or at least reduce them to an acceptable level in terms of navigational safety,” Mr Hood said.

Read the final report: Grounding of ABFC Roebuck Bay, on Henry Reef, Queensland, on 30 September 2017

Level crossing road surface

The derailment of a loaded coal train at a gravel level crossing west of Oakey, Queensland, shows the importance of an effective inspection and maintenance process for the approach roads and crossing surface at level crossings, a new ATSB investigation highlights.

ro2017007_news.jpg

On 21 July 2017, the underframe of a low-clearance heavy road vehicle very likely damaged both rails as it travelled over the private level crossing on the Western Line between Oakey and Jondaryan.

A member of the public saw the vehicle come to a sudden stop as it passed over the crossing, appearing to have “bottomed-out”. According to the witness, the driver exited the vehicle and inspected under the trailer, which was carrying a front-end loader, while it was stopped on the level crossing. The vehicle then continued on its journey.

Soon after, as the coal train approached the level crossing, the train driver noticed a ‘kink’ in both rails and attempted to stop the train.

The driver reported the lead locomotive shuddered as it passed over the crossing and he observed a number of wagons derailing as the train slowed. In all the train’s two locomotives and 18 coal wagons derailed, while there was damage to about 300 m of rail infrastructure.  

 “If rail infrastructure is damaged due to a road accident, it is vitally important that the driver responsible report the matter to the local police or the asset owner as soon as possible,” said ATSB Director Transport Safety Dr Stuart Godley.

“Rail infrastructure managers, who are responsible for the management of the rail corridor, need to ensure that approach roads and the crossing surface at level crossings are subject to regular and effective inspection and monitoring processes,” Dr Godley said.

“This is particularly relevant for level crossings with gravel-based road surfaces and inclined approach roads.”

Since the accident, track manager QR has installed a sealed asphalt surface on both sides of the level crossing. QR has also taken a series of actions to improve its inspection processes for level crossings.

Read the final report: Derailment of coal train, 8 km west of Oakey, Queensland, on 21 July 2017

Assess fatigue before flight

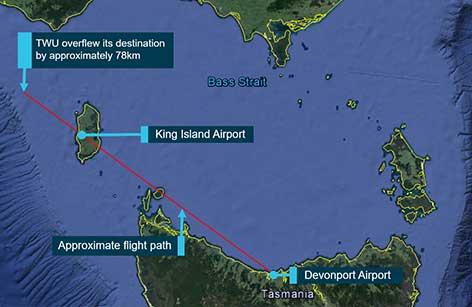
A pilot was experiencing acute levels of fatigue before falling asleep during an early morning freight flight from Devonport to King Island, an ATSB investigation has confirmed

ao2018075_news.jpg

The Piper PA-31-350 aircraft had reached top of descent into King Island when the pilot, who was the only person on board, started to feel tired and quickly fell asleep. After several unsuccessful attempts by ATC and other pilots in the area to contact the pilot, he awoke and advised ATC operations were normal and that he was turning back to King Island.

While on autopilot the aircraft had overflown the island by approximately 78 km to the north-west.

The aircraft landed without further incident. However, after talking with the operator, the pilot then flew from King Island to Moorabbin to complete his shift.

The ATSB found that the pilot had been awake for about 24 hours and had been unable to sleep during a scheduled rest period before the incident flight. Analysis confirmed the pilot’s fatigue was at a level known to effect performance, while further analysis showed that even if the pilot had been able to sleep during his rest period he still would have been fatigued to a level known to affect performance.

In addition, the pilot had not modified his sleep pattern in preparation for the planned night shift, contributing to his fatigue.

The ATSB found that the pilot had been awake for about 24 hours and had been unable to sleep during a scheduled rest period before the incident flight.

“This investigation highlights the need for pilots to assess their level of fatigue before and during their flight,” said ATSB Executive Director, Transport Safety, Mr Nat Nagy.

“Before commencing night operations pilots are encouraged to modify their usual sleep routines to ensure they are adequately rested.”

The ATSB also calls on operators to consider the risks of allowing a pilot to continue operating directly after a fatigue-related incident without corrective management.

“Just as it is the pilot’s responsibility to use rest periods to get adequate sleep and to remove themselves from duty if they feel fatigued, it is also incumbent on operators to implement policies and create an organisational culture where flight crew can report fatigue and remove themselves from duty in a supportive environment,” Mr Nagy said.

Information on fatigue management is available from the Civil Aviation Safety Authority(Opens in a new tab/window) and ATSB websites.

Read the final report: Pilot incapacitation involving Piper PA-31, VH-TWU, near King Island, Tasmania, on 8 November 2018

Wagon derails after axle failure

A freight train tanker wagon derailment after an axle failure due to an overstress crack highlights the importance of inspection techniques that detect fatigue cracking prior to failure, an ATSB investigation has found.

ro2017013_news.jpg

The primary occurrence that initiated the investigation was the 28 September 2017 derailment of a freight tanker wagon near Kimburra, Queensland. The wagon was part of the 730 metre long train 9T90, which comprised two locomotives and 52 GATX freight tanker wagons with a consignment of about 1.67 million litres of sulphuric acid.

The train crew were initially unaware of the derailment as it had no noticeable effect on the performance of the train. After travelling approximately 1,300 metres, upon seeing sparks from the derailed wagon, the driver applied the brake to stop the train gradually. There were no injuries and only minor damage to the track and rolling stock. There was no spillage of the train’s consignment.

The ATSB also analysed a second derailment, on 15 August 2018, involving the same type of wagon, finding that both derailments were the result of axle failure.

During the ATSB’s investigation a review of past failures and defects identified that the axle type was susceptible to fatigue cracking due to relatively minor damage that was not reliably detected prior to failure.

Effective axle inspection techniques that detect cracking prior to failure are fundamental to rail safety.

Rail axles are designed to have an infinite life and axles with undetected fatigue cracks that propagate to failure will usually result in a derailment. Axles should be resilient to fatigue cracking from in-service damage, and the ATSB’s safety message from this investigation highlights that effective axle inspection techniques that detect cracking prior to failure are fundamental to rail safety.

Following the 15 August 2018 derailment, rolling stock operator Incitec Pivot Limited (IPL) proactively inspected their entire GATX wagon fleet. Those inspections detected 17 cracked axles, and they were removed from service. IPL has also increased the frequency of inspections for the axle type while it replaces them with an improved version.

However, the ATSB has issued a Safety Recommendation to Aurizon, the company which conducts the inspections, to address the lack of using standard test pieces for checking test equipment. The ATSB acknowledges that Aurizon have taken proactive safety action to address anomalies in their inspection procedures, but the use of standard test pieces is an integral part of the relevant Australian Standard.

As such, the ATSB considers it represents best practice.

Read the final report: Derailment of acid train 9T90, near Kimburra, Queensland, on 28 September 2017

Keep alert while taxiing

The Australian Transport Safety Bureau (ATSB) reminds flight crews to remain alert and vigilant during taxiing, following an incident where a high workload situation probably led to an air traffic controller forgetting conflicting instructions had been issued.

ao2018040_news.jpg

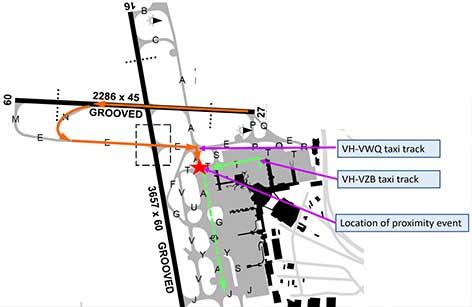
During the 30 April 2018 incident, an Airbus A321 airliner was taxiing to the gate after landing at Melbourne Airport when the captain had to brake heavily to avoid a possible collision with a taxiing Boeing 737-800. Both aircraft had been given clearance by the surface movement controller in the control tower to proceed through the same taxiway intersection.

While the ATSB’s investigation found several factors had increased the workload of the surface movement controller, this occurrence highlights the importance of flight crews remaining alert and vigilant during all phases of their flight, including taxiing. Separation of taxiing aircraft is a joint pilot and controller responsibility, and the timely action taken by the captain of the Airbus helped to avoid a potential collision.

During the morning peak period, the surface movement controller, who was conducting on-the-job training with a trainee air traffic controller at the time, was in the process of handing over the position at the end of shift to a relieving controller.

... this occurrence highlights the importance of flight crews remaining alert and vigilant during all phases of their flight, including taxiing.

Additionally, taxiway maintenance work had resulted in some taxiway closures. While the works were not directly related to the clearances issued to the two aircraft involved in this occurrence, they did reduce the efficiency of controlling taxiing aircraft, thereby increasing the controller’s workload.

The ATSB’s investigation highlights how increased workload and distraction can reduce performance and increase errors. For air traffic controllers, using tools and practices that reduce reliance on memory and delaying handovers until lulls in activity can mitigate these effects.

Read the final report: Taxiing proximity event involving Airbus A321, VH-VWQ and Boeing 737, VH-VZB, Melbourne Airport, Victoria, on 30 April 2018