Near collision

Key points:

  • Pilot of a PA-28 light aircraft did not sight an ATR airliner, which the controller had instructed them to follow
  • PA-28 turned in front of the ATR, resulting in a near collision
  • Pilots on both aircraft made incorrect assumptions about both each other’s movements
  • Controller did not seek confirmation from the PA-28 pilot that they understood the instruction to follow the ATR

A near collision where a Piper PA-28 training aircraft turned in front of an ATR72 regional airliner, reducing separation between the two aircraft to about 110 metres horizontally and 75 feet vertically, illustrates the dangers of making assumptions and having incomplete situational awareness, an ATSB investigation highlights.

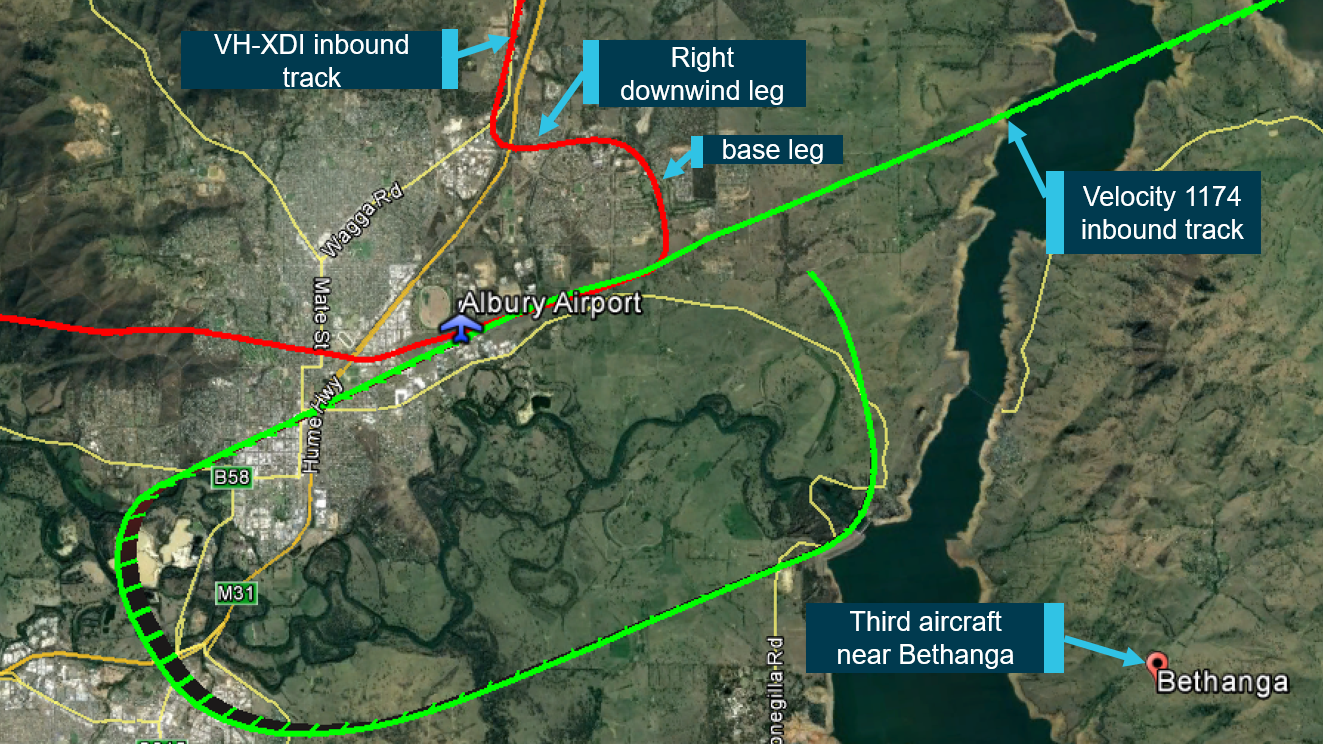
The Australian Airline Pilot Academy-operated PA-28, with a single student pilot on board, was conducting a navigation exercise to Albury from Wagga Wagga, NSW as part of the commercial pilot licence syllabus. On approach to Albury, air traffic control cleared the pilot to enter Albury (Class D*) airspace from the north. At the same time, a Virgin Australia Airlines ATR72 with two pilots, two cabin crew and 66 passengers on-board, was approaching Albury from the north-east, conducting a straight-in approach.

After the PA-28 had joined the downwind circuit leg for a touch-and-go landing on Albury’s runway 25, air traffic control informed the PA-28 pilot that ‘…you’re number two following an ATR on about a four‑mile final, report traffic in sight’.

The pilot acknowledged the instruction with the aircraft’s callsign, but did not read back any part of the instruction.

The controller later advised the ATSB that, due to their attention being focussed on a third aircraft, they were not monitoring the PA-28 as the aircraft continued on downwind and turned on to the base leg of the circuit. At that point the PA-28 pilot had not sighted the ATR nor advised the controller that they did not have it sighted.

Passing through approximately 600 feet above ground level, the ATR crew received a TCAS (traffic collision avoidance system) TA (traffic advisory) alert. They quickly identified the PA-28 below them and immediately commenced a missed approach.

The controller later reported not observing the near collision, and only shifted their attention back to the two aircraft when the ATR crew reported the missed approach. The controller advised that, as the ATR was already conducting a missed approach, they did not issue a safety alert.

The PA-28 pilot, meanwhile, advised the ATSB that when the ATR was first sighted it was so close that they lowered the nose of their aircraft to increase separation. The pilot recalled carrying out normal visual checks to ensure the base and final legs were clear, but did not look along the long final flightpath, assuming that the ATR, which had been cleared to land before the PA-28 joined downwind, was either on short final or had landed.

“As the PA-28 was operating under visual flight rules, separation between the two aircraft was the pilots’ responsibility, and the pilots on both aircraft made incorrect assumptions about both each other’s movements, rather than taking positive action to confirm that adequate separation would be maintained,” said ATSB Director Transport Safety Stuart Macleod.

“In addition, the air traffic controller had recognised the potential conflict and implemented a plan to sequence the aircraft’s arrival, however, the controller did not seek confirmation from the PA-28 pilot that they understood the instruction to follow the ATR.”

As well as finding that the PA-28 pilot did not sight the ATR, and did not advise the controller that they did not have the aircraft in sight before turning in front of the ATR, the ATSB’s investigation found the ATR flight crew were aware there was traffic in the area but did not assess the position of the PA-28 until the TCAS traffic advisory alert activated, Mr Macleod noted.

In addition, the investigation found that the controller did not identify the developing near collision as they were not effectively monitoring the aircraft in the circuit area due to their attention being focussed on another aircraft.

“The circumstances of this near collision incident illustrates the danger of assumption and incomplete situational awareness,” Mr Macleod said.

A number of safety actions have stemmed from the occurrence and the ATSB’s investigation, Mr Macleod noted.

“Virgin Australia and Airservices Australia have commenced discussions to convene a cross industry stakeholder meeting to include operators, the Civil Aviation Safety Authority, the ATSB and the broader industry to discuss the ongoing risk to operations at non‑controlled and Class D airports, such as Albury.”

Separately, AAPA conducted an internal investigation and implemented a number of additional risk controls, including the introduction of regular face-to-face seminars between controllers at Albury Tower and new students to explain operations in Class D airspace before students complete their first solo flight to Albury.

Read the final report: Near collision between Piper PA-28, VH-XDI and ATR72, VH-FVR, Albury Airport, New South Wales, on 19 October 2019

* Apart from runway operations, there is no separation standard required between VFR and IFR aircraft operating in Class D airspace, but flight crew are required to follow the instructions provided by controllers. An instruction given by a controller is to prevent collisions, however, separation between aircraft is the responsibility of flight crew. While not applying separation standards, controllers use separation methods to ensure aircraft do not conflict. Additionally, traffic information should be passed in situations where the controller considers pilots may be uncertain of the intentions of a second aircraft.

Aviation Occurrence Statistics (rates update) 2010 to 2019

Safety summary

Update

This statistical report shows aviation occurrence and activity data over the 10-year period from 2010–2019 to provide an insight into current and possible future trends in aviation safety. The previous edition (AR‑2020‑014) published in April 2020 presented 10 years of occurrence data, but aviation activity data was only available for 2014–2018 as 2019 activity data was not available at the time of publishing. This report is an update of the previous edition with the addition 2019 aviation activity data which also allows all occurrence rates to be presented for the period 2014–2019. This was done to present safety information to industry in a timely manner.

The purpose of this report

Each year, thousands of safety occurrences involving Australian aircraft and foreign‑registered aircraft operating in Australia are reported to the Australian Transport Safety Bureau (ATSB).

This report is part of a series that aims to provide information and statistical data to the aviation industry, manufacturers and policy makers, as well as to the travelling and general public, about these aviation safety occurrences. In particular, the data can be used to determine what can be learned to improve transport safety in the aviation sector.

Aviation activity data used in this report was all sourced from the Bureau of Infrastructure, Transport and Regional Economics (BITRE) which collects and compiles this data from reports submitted by airlines, and from other aircraft operators through its General Aviation Activity Survey.

This statistical report presents interactive web versions of all tables and graphs to allow the user to display aviation occurrence data in the format of their choice.

What the ATSB found

2019

In 2019, 222 aircraft were involved in accidents in Australia, with a further 155 aircraft involved in serious incidents (an incident with a high probability of becoming an accident). There were 35 fatalities from 22 fatal accidents. The number of fatalities was consistent with the average of the previous nine years (32.3 fatalities per year), and the number of fatal accidents was also consistent with its average (23.1 fatal accidents per year).

There have been no fatalities in scheduled commercial air transport in Australia since 2005.

2010 to 2019 accidents and incidents

Between 2010 and 2019, over 90 per cent of accidents and fatal accidents, and over 80 per cent of serious incidents, involved aircraft operating within the general aviation and recreational aviation sectors. In contrast, due to the more stringent reporting requirements for air transport operations, three‑quarters of reported incidents involved aircraft operating within commercial air transport.[1]

Considering all years in the period, the number of general aviation (GA) fatalities and fatal accidents decreased. The number of fatalities and fatal accidents within commercial air transport and recreation aviation remained relatively constant.

Since 2016, remotely piloted aircraft (RPA) have surpassed helicopters to become the second most common aircraft type involved in an accident. However, over this period (2016–2019) there were no injuries involving an RPA, whereas there were 16 fatal, 30 serious, and 44 minor injuries resulting from an occurrence involving a helicopter.

Further, the number of manned aircraft experiencing near encounters with an RPA also increased significantly over the study period.

2014 to 2019 accident rates

Statistics in this report have been organised around the type of aircraft activity being conducted, rather than the operational regulation. Due to the availability of activity data (departures and hours flown data), it was only possible to calculate accident and fatal accident rates over the six‑year period 2014–2019.

Over this period, test and ferry flights, recreational flights involving an aircraft registered with Recreational Aviation Australia (RAAus), followed by pleasure and personal transport, had the highest accident rates. Community services flights, followed closely by test and ferry flights, had the highest fatal accident rates. (However, as there was only one fatal accident involving an aircraft conducting community service flights between 2014 and 2019 there is a high level of statistical uncertainty associated with this rate). For aircraft types, recreational aeroplanes, followed by commercial balloons had the highest accident rates. Also, recreational aeroplanes had the highest fatal accident rate.

Commercial air transport

There were no fatalities within commercial air transport in 2019.

Over the full study period (2010–2019), more than half of all serious incidents and the majority of accidents and fatal accidents for commercial air transport operators involved aircraft conducting non‑scheduled activities, predominantly passenger transport charters. There were no identified increases or decreases in the number of accidents or serious incidents, however, the number of reported incidents for aircraft conducting scheduled international flights and commercial freight increased over the 10 years.

Between 2014 and 2019, around three‑quarters of the hours flown, and approximately one‑half of all departures, within commercial air transport, were operated by scheduled domestic or international operations.

Concerning activities within commercial air transport, passenger transport charters had the highest accident and fatal accident rates (per hour flown). However, commercial freight had the higher number fatal accidents per departure.

For specific aircraft types, within commercial air transport, balloons had an accident rate (between 2014 and 2019) more than 10 times higher than for aeroplanes or helicopters. However, there was only one fatal accident involving a commercial balloon in the 2010 and 2019 timeframe.

Most commercial accidents and serious incidents were operational in nature (typically aircraft control and terrain collisions). The majority of incidents were environmental (mainly birdstrikes).

General aviation

In 2019, there were 17 fatalities in GA.

Over the 10 years, around one‑third of GA accidents and 45 per cent of fatal accidents involved aircraft conducting sport and pleasure flying. Aerial work accounted for a further 37 per cent of GA accidents and 33 per cent of fatal accidents. The number of GA accidents per year increased over the period, with aerial work identified as the primary contributor. Conversely, there was a decrease in the number of fatal accidents, resulting in a decrease of around one fatal accident, or 1.4 fewer fatalities, per year.

There was also an increase in the number of reported incidents for GA aircraft conducting instructional flying.

Between 2014 and 2019, around 40 per cent of GA hours flown were conducted within aerial work, with instructional flying accounting for a further 30 per cent. Sport and pleasure flying made up around 14 per cent.

The rate of GA accidents decreased over the six years 2014–2019. The main contributors to this decline were sport and pleasure flying, and own business travel.

Between 2010 and 2019, there was an increase in the number of GA RPA accidents per year; this primarily resulted from a significant increase in the overall number of survey and photographic accidents.

Overall, there was a decrease in the accident rate for aeroplanes conducting GA flying. The main contributors to this decrease were identified as aeroplanes conducting sport and pleasure flying, and own business travel.

Over the 10 years, the majority of GA accidents, incidents and serious incidents were related to operational or technical issues. Additionally, the majority of fatal accidents were also attributable to operational issues.

Further, the number of GA operational-related accidents and serious incidents, per year, increased over the period. Instructional flying was the main contributor to this operational-related increase. Additionally, there was an increase in the number of accidents and serious incidents of a technical nature; largely attributable to aerial work operations (especially those conducted using an RPA).

Recreational aviation

In 2019, there were 18 fatalities involving an aircraft conducting recreational flying.

The accident rate for recreational flying decreased between 2014 and 2019, with Recreational Aviation Australia (RAAus) registered aircraft having the greatest contribution to this reduction.

Aeroplanes had the highest accident and fatal accident rates of any recreational aircraft type.

Similar to GA, over the full study period (10 years), the majority of recreational accidents and serious incidents were operational (mainly terrain collisions) or technical (primarily engine failure or malfunction) in nature.

__________

  1. Includes scheduled airline flying as well as non-scheduled passenger-carrying activities such as charter, medical transport, and joyflight/sightseeing charters, as well as freight

Publication details

Investigation number AR-2020-047
Publication type Research and Analysis Report
Publication mode Aviation
Publication date 04/11/2020
Subject matter Aviation statistics

Flight control confusion

Key points:

  • Cessna 152 entered a steep dive after student pilot released control wheel during pitch trim demonstration
  • Instructor sustained minor injuries and aircraft sustained structural damage during recovery
  • Instructors need to account for the potential for students to carry out unexpected actions

A Cessna 152 abruptly pitched down and entered a steep dive when a student pilot released the aircraft’s control wheel during a demonstration of the effects of control and the use of trim, an ATSB investigation details.

The Basair Aviation College-operated Cessna 152 had departed Brisbane’s Archerfield Airport on 28 May 2019 with a student pilot on their first flight and an instructor on board to demonstrate manoeuvres from the effects of control flight training syllabus.

With the student flying, the aircraft was approaching overhead Lagoon Island south-east of Brisbane at about 2,000 feet above ground level when the instructor moved the pitch trim to about two-thirds travel nose down while the student maintained attitude with nose-up pressure on the control wheel.

“When returning the elevator trim to neutral, the student became confused about the correct procedure and suddenly released the control wheel and the aircraft rapidly pitched nose-down, rolled left, and entered into a dive,” said ATSB Director Transport Safety Dr Mike Walker.

“The instructor took control of the aircraft and arrested the descent 25 seconds later, at about 400 feet. Flight radar data showed the aircraft experienced an average descent rate of over 3,000 feet/minute.”

The instructor, who sustained minor injuries, then terminated the lesson and returned to Archerfield. 

A post-flight examination of the aircraft identified significant structural damage with bending and buckling of the right horizontal stabiliser structure, likely due to excessive asymmetric flight loads from the dive recovery.

“The instructor’s use of a large amount of nose-down elevator trim for the lesson increased the effect when the student released backpressure on the elevator, leading to a sudden nose-down pitch change and subsequent entry into a dive,” Dr Walker said.

The investigation report notes that the flying school’s instructor guide did not specify a limit of trim input for such exercises.

“The ATSB also determined that the instructor’s hands were not in a ready position to take control in the event of any mishandling by the student pilot,” Dr Walker said.

“The recovery by the instructor was likely further delayed after sustaining a head injury during the in-flight upset, and initially being unsure about what had happened and how to then recover the aircraft.”

Following the incident the flying school operator revised its training procedures to include detailed instructor demonstrations prior to student practice of effects of control manoeuvres, and to ensure the use of a consistent moderate amount of trim following the incident.

“The first stages of flight training can be both exciting and daunting and this incident serves to remind student pilots to raise with their instructor any uncertainties they have over procedures,” Dr Walker stated.

“Conversely, instructors need to account for the potential for students to carry out unexpected actions. This means that lessons should be conducted under the lowest risk conditions that still impart the lesson intent.”

Read the final report: Loss of control involving Cessna 152, VH-JIW, 34 km east-south-east of Archerfield Airport, Queensland, on 28 May 2019

Low rotor RPM at low height

Key points:

  • The helicopter’s rotor RPM began to decay and the pilot initially did not apply full throttle
  • The pilot attempted a forced landing, but was unable to arrest the rate of descent, resulting in a hard landing and injuries
  • Low rotor RPM may develop in various flight conditions, but it is the low airspeed-low height condition that is most likely to result in an accident

The Australian Transport Safety Bureau (ATSB) reminds all helicopter pilots to be prepared and respond immediately to low rotor RPM warnings, following the investigation into the collision with terrain of a Robinson R44 helicopter south of Ayers Rock Airport, Northern Territory, on 17 January 2018.

Shortly after departing the Yulara Town helipad for a 15-minute scenic flight with the pilot and three passengers onboard, the helicopter’s rotor RPM began to decay and the low rotor RPM warning activated. Following this warning, the pilot initially did not apply full throttle (for at least 5 seconds), and lower the collective lever sufficiently to stop the helicopter climbing.

The helicopter continued flight for about another 90 seconds, climbing to about 200 feet at a low airspeed. This resulted in the rotor RPM decaying further to a level from which the pilot could not recover. The pilot attempted a forced landing, but was unable to arrest the rate of descent, resulting in a hard landing. The pilot and two passengers were seriously injured, with the third passenger sustaining minor injuries. The helicopter was substantially damaged.

Transport Safety Investigators found that the take-off was conducted at a high density altitude at near maximum weight. Therefore, a high engine manifold pressure (MAP) would be expected for the take-off. However, passenger video evidence indicated the rotor RPM decay started at a relatively low MAP, and that the MAP increased slowly as the RPM steadily decayed.

The ATSB’s investigation concluded that the helicopter's rotor RPM steadily decayed due to a likely limited opening of the engine throttle during take-off. Fine-tuning of the engine throttle is controlled automatically by the engine governor, but it can be manually overridden by the pilot. The reason for the limited opening of the throttle could not be determined.

“Low rotor RPM may develop in various flight conditions, but it is the low airspeed-low height condition that is most likely to result in an accident,” acting Director Transport Safety Kerri Hughes said.

“Helicopter pilots should ensure they are familiar with the power curve, the associated airspeeds for their particular helicopter, and be prepared to respond immediately to a low RPM warning.”

Further, the investigation established that the pilot had inadvertently adopted a practice of conducting rotors running turn-arounds (for passenger transfers) with the governor switched off. This was not in accordance with the manufacturer’s checklist requirement for the governor to remain on from start until shut-down, nor the operator’s procedure for the governor to be selected on for the engine run-up.

“Although the pilot reported that the governor was selected on and checked before lift-off, this practice increased the risk of an inoperative governor not being detected before take-off,” Ms Hughes said.

The operator, Professional Helicopter Services, used individual passenger weights for their loading calculations, which was considered best practice. However, it was found that the operator’s passenger scales were not calibrated and were under-reading the actual occupant weights.

“This resulted in the helicopter operating at a higher weight than planned, but less than the maximum weight,” Ms Hughes said.

“While the operating weight was within the published limits, the under-reading scales increased the risk of their helicopters not achieving their take-off performance.”

The ATSB has issued a safety recommendation to the Robinson Helicopter Company to review the R44 pilot's operating handbook low rotor RPM recovery procedure for consideration to include a reference to the minimum power airspeed (Vy) for pilot awareness. Robinson reported that this will be reviewed by engineering staff for possible revision to the pilot operating handbook.

Read the final report: Main rotor speed decay and forced landing involving Robinson R44, VH-HGX, 5 km south Ayers Rock Airport, Northern Territory, on 17 January 2018

Collision with level crossing gates

Key points:

  • Train driver commenced braking slightly earlier than would normally be the case due to the wet and windy weather conditions
  • Train passed through crossing at 93 km/h and collided with level crossing gates, after being unable to stop at Ballarat Station
  • Investigation is on-going

A VLocity passenger train was travelling at 93km/h when it struck and destroyed heritage-listed swing level crossing gates at Ballarat, Victoria on 30 May 2020, a preliminary report confirms.

The V/Line VLocity passenger train, with a train driver, conductor and two passengers on-board, was operating an evening service from Melbourne’s Southern Cross Station to Wendouree in Ballarat’s west when it was unable to come to a stop at Ballarat Station, the preliminary report from the on-going transport safety investigation details.

“Departing Ballan, the driver began to experience wheel slip events during powering and as the journey progressed, experienced instances of wheel slide during braking,” said Chris McKeown, Victoria’s Chief Investigator, Transport Safety (CITS).

These wheel slip events triggered the train’s Wheel Slip/Slide Protection (WSP) system, which activates when a train’s powered axles are rotating faster than its non-powered axles.

If a wheel slide occurs during braking, brake cylinder pressure is reduced to regain the right braking effort for the available wheel adhesion and sand is applied to the rail to improve wheel traction.

“On the approach to Ballarat, the driver reported having commenced braking slightly earlier than would normally be the case due to the wet and windy weather conditions,” Mr McKeown said.

The train’s event recorder detected braking being initiated with the train 4.9 km from Ballarat Station and the train travelling at approximately 160 km/h, followed by indications of wheel-slide and a series of brake applications and activation of the train’s sanding valve.

“An emergency brake application was applied 235 metres before the train’s intended stop at Ballarat Station,” Mr McKeown said.

“The train travelled through Ballarat Station at 100 km/h and passed a Departure signal at Stop as it headed towards the Lydiard Street North crossing.”

One second before the train passed through the crossing, the crossing’s road traffic lights changed from green to flashing amber. However, the gates were still across the track rather than protecting the crossing from road traffic when struck by the train.

CCTV footage showed that approximately 49 seconds before, a group of three pedestrians passed over the crossing.

The train subsequently passed through the Doveton Street level crossing and came to a stop approximately 600 metres west of its intended stopping point. A passenger who had been standing near an exit door as the train approached Ballarat Station sustained head, back, and leg injuries, and was taken off the train by emergency services and admitted to hospital.

“The on-going investigation will examine a range of factors including operation and maintenance of VLocity sanders, track condition, dynamic performance of the braking system, train operation and performance,” Mr McKeown noted.

Subsequent to the accident, testing identified performance issues with the VLocity 3VL70 train’s sanding system and manufacturer Bombardier has subsequently undertaken fleet-wide testing of VLocity sanders and performed remedial action where required.

Mr McKeown noted that the investigation’s preliminary report does not contain findings, identify contributing factors or outline safety issues, which will be detailed in the final report.

The Chief Investigator, Transport Safety (CITS) conducts rail investigations in Victoria on behalf of the ATSB under the Transport Safety Investigation Act 2003.

Read the preliminary report: Collision of passenger train 8185 with level crossing gates, Lydiard Street North, Ballarat, Victoria, on 30 May 2020

Runway incursion

Key points:

  • 737 taxied toward active runway; second 737 rejected take-off
  • Taxiway location and design significantly increased the risk of a runway incursion
  • Runway incursions are a significant risk to safe aviation operations and a key global safety priority

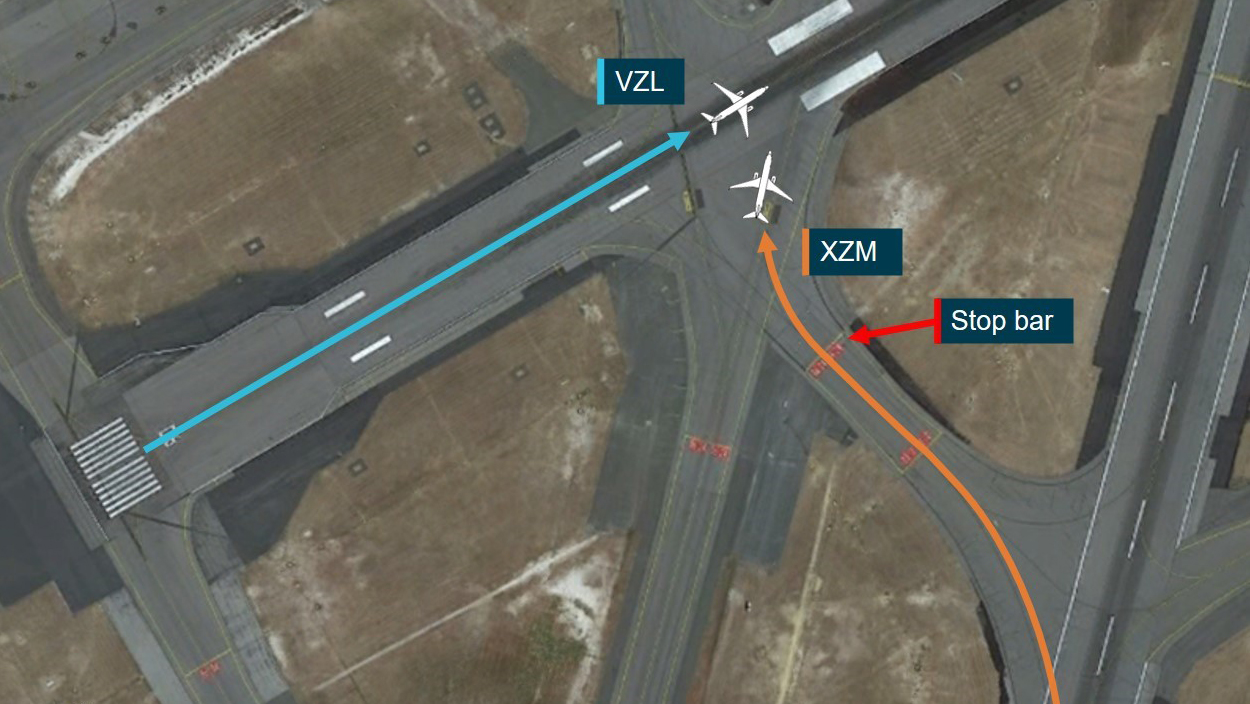
The crew of a Boeing 737 had to reject their take-off roll when a second 737 did not stop at a holding point and passed through an illuminated stop bar after landing at Perth Airport, an ATSB investigation report details. 

On 28 April 2018, a Qantas Boeing 737, registered VH-XZM, landed on runway 03 at Perth, exiting the runway onto taxiway J2, which led to a holding point for crossing runway 06. The aircraft did not stop at the holding point and crossed an illuminated stop bar (a set of lights embedded across the taxiway surface) without an air traffic control clearance.

At that time, a second Qantas 737, VH-VZL, had commenced its take-off roll from runway 06. An automated warning within the Perth air traffic control tower alerted the aerodrome controller (ADC) of the stop bar violation and the controller issued an instruction for the departing 737 to ‘stop immediately’.

Soon after, the flight crew of VH‑XZM became aware of their position and stopped their aircraft just before crossing the edge of runway 06. VH-VZL’s wingtip passed about 15 metres from VH-XZM’s nose at low speed just before coming to a stop.

Among other findings, the ATSB found that the captain of VH-XZM was not expecting to cross runway 06, having developed an incorrect mental model of their location and thinking the aircraft was on taxiway J1 which led directly to the terminal area.

“Due to this incorrect mental model, and a combination of workload and distractions at key times, the flight crew did not detect the runway crossing issue until their aircraft had almost reached the edge of runway 06,” said ATSB Director Transport Safety Dr Mike Walker.

Taxiway J2 was the preferred runway exit for jet aircraft landing on runway 03, the ATSB’s investigation report notes.

“The location and design of the taxiway significantly increased the risk of a runway incursion onto runway 06/24,” Dr Walker said.

“The relatively shallow intersection angle with the runway and wide turn radius meant pilots were more likely to take the exit at a higher speed, and this combined with the short distance to the holding point gave pilots less time to see the illuminated stop bar lights at the runway holding point and stop.”

Although the junction around taxiway J2 was identified as a ‘hot spot’ on aerodrome charts, there was no detailed information about the reasons for it.

Also, Qantas did not specifically require pilots to brief hot spots during departure and approach briefings.

In response to the runway incursion, Airservices Australia made taxiway J2 unavailable for use, and Perth Airport subsequently removed taxiway J2 from aerodrome charts.

In addition, Airservices changed the settings of an alerting system to ensure tower controllers at Perth Airport performing multiple roles received appropriate aural and visual alerts at their workstation.

“Runway incursions are one of the most significant risks to safe aviation operations and a key global safety priority,” Dr Walker said.

“Airport operators and local runway safety teams are strongly encouraged to identify and mitigate the risk of hot spots, especially those that involve short distances between runways, complicated junctions, and the potential for higher taxi speeds.”

Since the incident, Qantas published a safety information notice to all pilots containing information about the background of runway incursions. The airline also updated its Flight Administration Manual to include a requirement for pilots to brief relevant airport hot spots and their contingency planning to mitigate against the possibility of collision or runway incursion.

“Pilots can help prevent incursions by identifying runway hot spots during departure and approach briefings, and discussing the actions they will take to reduce the risk of a runway incursion,” Dr Walker said. 

“The ATSB also strongly encourages air traffic controllers to provide safety alerts and/or clear instructions – such as ‘stop immediately’ – to the flight crews of all aircraft involved in runway incursions and related occurrences.”

Dr Walker noted that the aerodrome controller and flight crew of VH-VZL exhibited a high level of situational awareness to respond to the incursion.

Read the final report: Runway incursion involving Boeing 737, VH-XZM, resulting in a rejected take-off involving Boeing 737, VH-VZL, Perth Airport, Western Australia, on 28 April 2018

Sudden control input

Key points:

  • A sudden wind change during high-speed descent resulted in the airspeed suddenly increasing towards the aircraft maximum operating speed
  • The captain responded by abruptly pulling back on the control column, causing autopilot to disconnect
  • Subsequent sudden pitch attitude and vertical acceleration changes resulted in injuries to cabin crew members.

The actions of the captain of a Boeing 737 in response to a sudden speed increase during a high speed descent resulted in sudden pitch changes and injuries to two cabin crew members, a new ATSB report details.

The Virgin Australia-operated Boeing 737-800 was at the top of the descent 136 nautical miles south-east of Adelaide Airport conducting a scheduled passenger flight from Melbourne on 13 September 2017, with the first officer acting as pilot flying.

Air traffic control instructed the crew to perform a high-speed descent, which they commenced with the autopilot engaged with a target descent speed of 320 knots, which was higher than the normal descent speed of 280 knots.

During the descent, the first officer attempted to manage airspeed by using changes in the autopilot modes and reductions in the target airspeed. As the aircraft descended through around 17,000 feet, the tailwind affecting the aircraft decreased suddenly and significantly, which caused the indicated airspeed to increase and approach the maximum operating speed limit of 340 knots.

Highly concerned about overspeeding the aircraft, the captain responded by abruptly pulling back on the control column, causing the autopilot to disconnect. The resulting control forces caused sudden changes to the aircraft’s pitch attitude and vertical acceleration.

Two cabin crew members who were standing in the aircraft’s rear galley eating a meal received injuries during the upset, with one sustaining a broken leg.

ATSB Director Transport Safety Dr Stuart Godley said that during the occurrence, the aircraft only exceeded its maximum operating speed by one knot, which did not require any structural inspections to ensure the ongoing airworthiness of the aircraft. Instead, the safety implications associated with this event related to the actions of the captain in response to the sudden change in airspeed.

“Even though the autopilot was operating correctly, when the aircraft was approaching and exceeding the maximum operating speed, the captain’s perception was that the autopilot was not controlling the aircraft and that urgent intervention was necessary,” Dr Godley said.

“However, the captain did not follow the normal procedure for taking over control of pilot flying duties, and the large pitch control inputs made by the captain were probably influenced by a perception of urgency.”

Dr Godley said the investigation serves to remind pilots that they are entitled to decline air traffic control instructions where they do not perceive they can safely comply.

“Due to increased kinetic energy and reduced margins to placard speed limits, high-speed descents involve a higher level of risk, including increased risk of harm due to abrupt control input.”

The investigation also highlights the challenges pilots face when responding to sudden or unexpected situations, Dr Godley said.

“There will often be a reduction in safety when pilots perceive a situation is urgent and when they make decisions rapidly and reflexively. In these situations, pilots may not be able to effectively process information or make good decisions.”

The investigation also notes that it took over 90 minutes for the injured cabin crew member, who had sustained a badly broken leg, to be removed from the aircraft after its arrival at Adelaide, while the operator’s ground operations supervisor, Aviation Rescue Fire Fighting Service (ARFFS) officers and SA Ambulance officers co-ordinated the extraction.

The injured cabin crew member was not able to walk or to sit in a wheelchair, and an ambulance stretcher would not fit down the aircraft aisle, however, the ground operations supervisor declined an ARFFS request to use a catering truck, the report notes.

Instead, emergency services personnel used a slide sheet to drag the injured cabin crew member along the aisle to the front of the aircraft, then placed the injured cabin crew member on a stretcher.

Virgin Australia has subsequently updated the training and information provided to pilots about overspeed and overspeed recovery. The airline has also changed procedures for ground handling staff when responding to requests from emergency services.

Read the final report: Overspeed and pitch up resulting in cabin crew injury involving Boeing 737, VH‑VUE, 42 NM east-south-east of Adelaide Airport, South Australia, on 13 September 2017

Pseudo-sat in-flight break-up

Key points:

  • Unstable atmospheric conditions resulted in UAV being unable to maintain controlled flight
  • UAV’s structural limitations were exceeded, resulting in both wings fracturing at about mid-span
  • Procedures ensured minimal risk to the public and environment

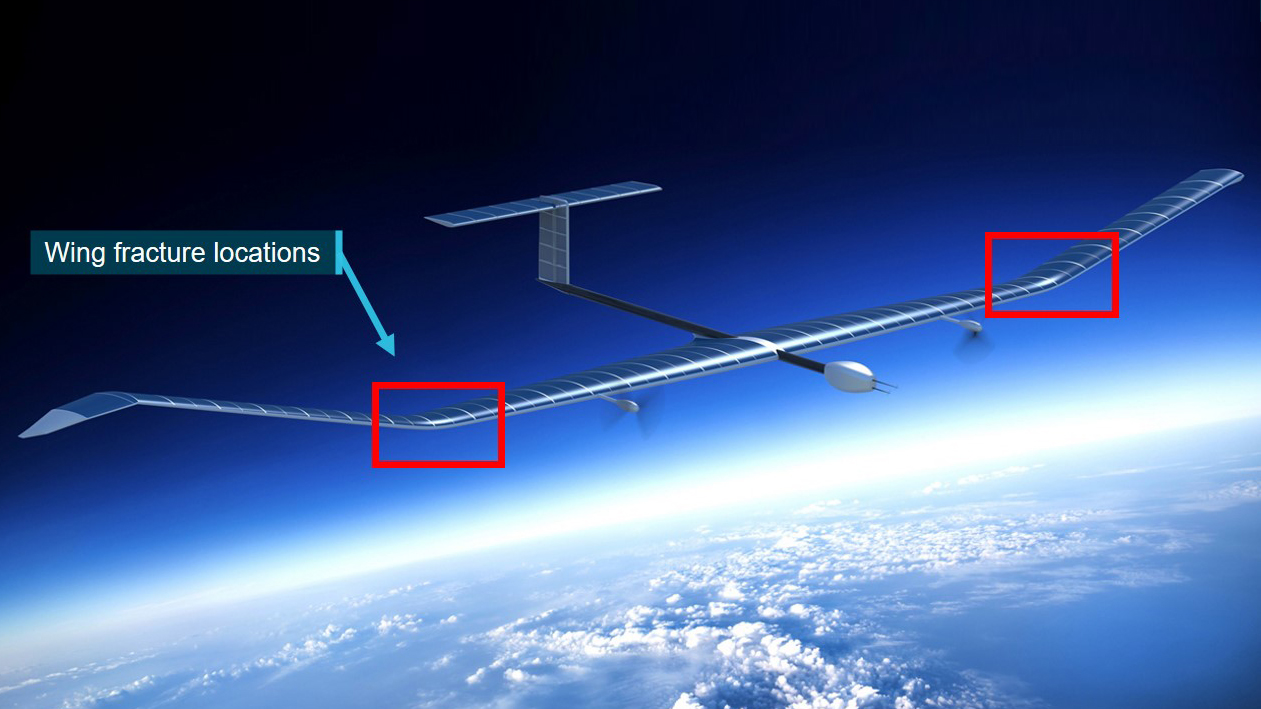
An Airbus Zephyr high-altitude UAV broke up in-flight after encountering unstable atmospheric conditions which resulted in a series of uncommanded rolls and an uncontrolled spiral descent over remote northern Western Australia, a new ATSB report details. 

The Zephyr unmanned aerial vehicle (UAV), designed as an ultra-light high-altitude pseudo‑satellite, had launched from Wyndham Airport on 28 September 2019 for a high altitude flight.

While climbing through an altitude of 5,200 feet and about one hour after launch, the UAV encountered unstable atmospheric conditions that resulted in an uncommanded roll to the right and a track change of about 180° before self-recovery. The flight crew in the ground control station, comprising a remote pilot, a remote pilot in command, a mission planner and a flight test engineer, elected to continue the climb and directed the UAV towards the north in anticipation of smoother conditions.

However, atmospheric conditions became increasingly unstable and the UAV, as it passed through 8,700 feet, experienced a second uncommanded roll but again was able to self-correct, with the crew increasing power and directing the aircraft to calmer conditions. Wind conditions reduced groundspeed to around 1 knot, reducing its ability to move out of the unstable conditions in a timely manner, and the Zephyr descended about 1,000 feet over the next 7 minutes.

The UAV then experienced a third uncommanded roll to the right. Unable to self‑recover, the UAV entered into an uncontrolled spiral descent, during which its maximum airspeed was exceeded and the roll angle increased beyond its structural limitations, resulting in both wings fracturing at about mid-span.

ATSB acting Director Transport Safety Derek Hoffmeister noted that the solar-electric Zephyr was designed to operate in the stratosphere, above the weather and conventional air traffic, and was extremely sensitive to atmospheric instability during the climb and descent phases.

“Once the Zephyr entered an area of unstable atmospheric conditions that exceeded the aircraft's ability to remain in the flight envelope, an in-flight break-up occurred,” Mr Hoffmeister said.

A separate Zephyr UAV was involved in an accident after launching from Wyndham in March 2019. The September 2019 accident was only the second launch from Wyndham for the Zephyr program.

“At the time of the occurrence, the Zephyr program was in its early operation phase. As such, information regarding the UAV’s structural limitations and methods to forecast turbulence were still evolving,” Mr Hoffmeister said.

“However, operational and post-crash management procedures were effective in minimising risk to the public and environment.”

In response to this accident, Airbus conducted an investigation of this occurrence, which resulted in several safety recommendations being directed to the design and operational departments of the Zephyr program.

“The number of UAVs and remotely piloted aircraft in Australia, and worldwide, is increasing rapidly," Mr Hoffmeister said.

“Through reporting and investigation of UAV and remotely piloted aircraft accidents and incidents, the ATSB is able to monitor trends and identify areas for safety improvement.

“This information helps to enhance the safety of all aircraft, and the public in general, enabling this sector of the aviation industry to continue to grow and develop.”

Read the final report: In-flight break-up involving Airbus Zephyr unmanned aerial vehicle, near Wyndham Airport, Western Australia, on 28 September 2019

Freight train wagons runaway

Key points:

  • Wagons started to roll back to towards siding as freight train’s locomotives started run-around movement
  • Brake pipe air taps were closed during wagon uncoupling before full application of train air brakes
  • Handbrakes not applied to wagons

Thirty freight train wagons rolled away unattended for 1,425 metres from a crossing loop before slowing and coming to a stop just before the end of a siding, road and level crossing at Bordertown, South Australia on 23 November 2019, a new ATSB report details.

The Bowmans Rail-operated freight train was being moved out from the siding onto the crossing loop, where locomotive drivers involved in preparing the train for its journey to Adelaide detached the train’s two locomotives for a run-around movement to reattach the locomotives to the other end of the train’s consist.

As the runaround movement started, the unattended wagons started to roll back towards the siding. The wagons rolled over a level crossing, bounced over a derailer and continued back into the siding. A driver in the siding saw the rolling wagons and ran alongside and commenced applying the handbrake to one of the wagons before they slowed and came to a stop.

In total, the wagons rolled unattended for about 1,425 metres, before stopping about 47 metres from the end of the siding, immediately before a level crossing.

“The ATSB found that while detaching the locomotives a misunderstanding between the driver in the lead locomotive and the driver uncoupling the wagons led to the brake pipe air taps being closed out of sequence and before a full application of the trains air brakes had propagated to the wagons,” said ATSB Director Transport Safety Dr Stuart Godley.

In addition, handbrakes were not applied to any wagons, the report notes. Not applying handbrakes during the run-around at Bordertown had become a common practice, as it saved time and had not caused any issues in the past.

“Once the locomotives were detached, the lack of air brakes and handbrakes allowed the wagons to roll away on the descending grade.”

Dr Godley said the occurrrence highlights how omitting a procedural step may result in over-reliance on remaining protective measures.

“The non-application of handbrakes increased the train’s reliance on the full application of wagon air brakes to prevent a runaway,” he said.

“However, a slight out of sequence implementation of the air brake process resulted in only partial application of the wagon air brakes and the subsequent runaway of unattended wagons.

“It is essential that all procedural steps are undertaken when uncoupling wagons for run-around movements.”

In response to the incident, operator Bowmans Rail has issued a safety alert requiring uncoupled wagons to have all air exhausted and handbrakes applied when left unattended.

“Additionally, the operator has communicated the findings of their investigation and their expectations to train crew, as well as consulted on improvements planned for its Bordertown shunting processes,” Dr Godley said.

The ATSB also found that the baulk installed on the Bordertown siding before the road and level crossing was only suitable for restraining runaways at speeds of up to 1.5 km/h and was unlikely to restrain the speed and momentum of a faster runaway.

The Australian Rail Track Corporation has since installed an arrestor bed on the track at the Bordertown dead end.

Read the final report: Runaway of freight train wagons, Bordertown, South Australia, on 23 November 2019

Level crossing protections

Key points:

  • Level crossing protections mistakenly removed during signal upgrade work
  • Isolation plans did not provide specific detail for the scope of work for each stage of the project
  • Investigation highlights the importance of providing clear, concise and detailed work instructions to reduce the risk of errors

Flashing lights and boom gates were not activated at a North Geelong level crossing when an Overland passenger train passed through as protections had been inadvertently removed for planned track work.  

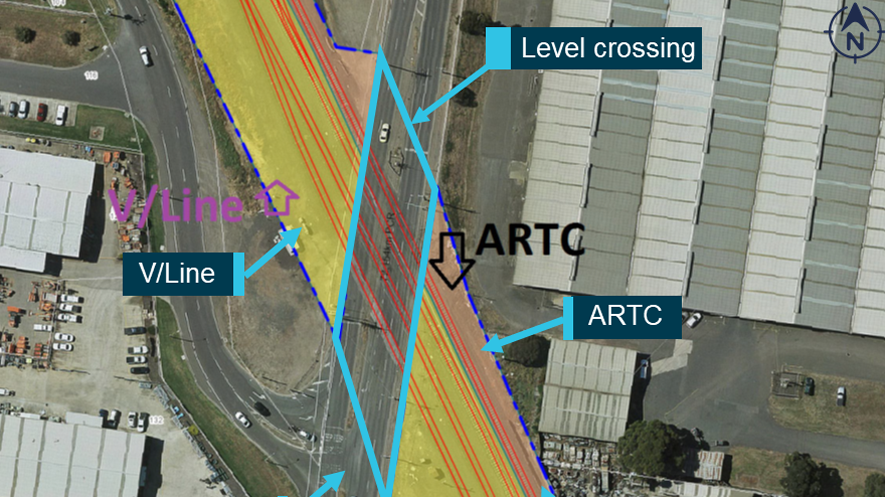
An ATSB investigation report into the 8 January 2019 incident found that, in preparation for signalling upgrade works, the Thompson Road level crossing was to be isolated for the broad and dual-gauge tracks only. However, the level crossing protections for the adjacent standard-gauge track were also deactivated.

“Level crossing protections for the standard-gauge track, as used by the Overland passenger train service, was to continue operating as normal until a second stage of works at the site at a later date,” said acting ATSB Director Transport Safety Kerri Hughes.

“However, the signalling tester, following the provided isolation plans, mistakenly isolated the level crossing for an upcoming second stage of works at the same time as for the initial stage of works.”

As a consequence, as the Adelaide-bound Overland service 3MA8 approached the level crossing, the train crew noticed that the flashing lights had not activated and the boom gate had not lowered. In response, they commenced braking, reduced the throttle, and sounded the horn to alert approaching road traffic.

“The train passed through the crossing at a reported speed of about 50 km/h, with the level crossing protections inactive,” said Ms Hughes.

“Although there was road traffic in the vicinity, no vehicles were on the crossing at the time the train passed through.”

The signalling upgrade work, managed by VicTrack and contracted to UGL Engineering, involved the removal, modification and installation of new signalling equipment. Stage one of the project involved the isolation of crossing protections for the V/Line-managed broad-gauge and dual-gauge tracks, with the level crossing protections for the adjacent ARTC-managed standard-gauge track to operate as normal until the start of a second stage of works.

The ATSB found that there were no supporting instructions in the plan specifically detailing the scope of work for each stage. 

“The contractor undertaking the work did not provide signalling testers with specific instructions detailing the scope of work to be conducted at each stage of a project, but rather, only provided packaged isolation plans for the entire project,” Ms Hughes said.

“The absence of these instructions increased the risk of the works being incorrectly implemented.”

This investigation highlights the importance of providing clear, concise, and detailed work instructions to reduce the risk of errors during critical safety work, Ms Hughes noted

“Work instructions are step-by-step guides on how to perform a specific task or activity, in support of a process or procedure. They are important defences within a safety system for ensuring work is performed safely and as intended.”

In response to the incident, VicTrack now includes specific work instructions for each task associated with level crossing isolation plans.

Read the final report: Level crossing irregularity involving passenger train 3MA8, North Geelong, Victoria, on 8 January 2019