Loss of engine power

The importance of having a clear, defined emergency plan for critical stages of flight is highlighted by a Cessna 172’s loss of control and collision with terrain in a residential street near Melbourne’s Moorabbin Airport, an ATSB investigation notes.

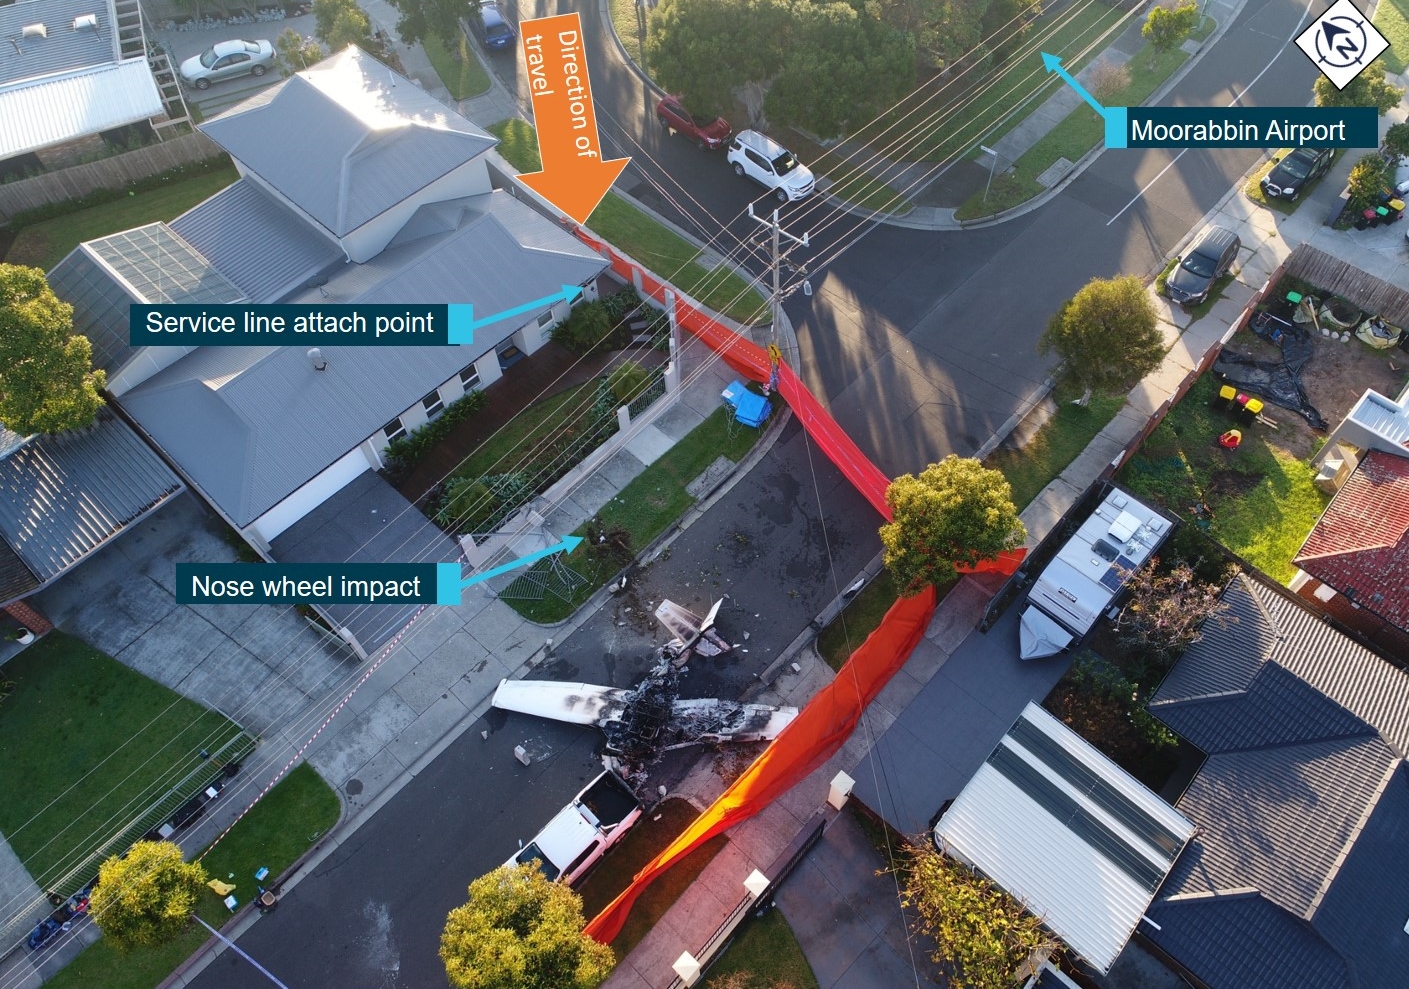
Cessna 172S, registration VH-EWE, was returning to land at Moorabbin Airport on 8 June 2018. The private flight was being conducted following maintenance, which included a scheduled engine change. The pilot, and sole occupant, was also one of the licenced aircraft maintenance engineers that had conducted some of the recent maintenance on behalf of the aircraft owner.

While the aircraft was on final approach to runway 35 Left, and at about the time it was cleared to land, witnesses on the ground observed the aircraft a little lower than expected and described hearing the engine ‘spluttering’, ‘struggling’, and that it ‘sounded like a lawn mower struggling to start’.

The pilot transmitted a MAYDAY call, stating ‘we’ve got engine failure.’ Witnesses observed the aircraft’s nose and left wing drop, consistent with an aerodynamic stall. The aircraft collided with terrain in a residential street about 680 metres from the airport. The pilot was fatally injured and a post-impact fuel-fed fire destroyed the aircraft. There was minor damage to a house perimeter fence and a parked car. No one on the ground was injured.

Taking positive action and ensuring that control is maintained has a much better survivability potential than when control of the aircraft is lost.

“The loss of engine power while on final approach presents a scenario where there may be limited forced landing options, especially when there is insufficient height to glide to the airport,” said ATSB Director Transport Safety Stuart Macleod.

“This is particularly relevant where the approach is over built-up areas, such as at Moorabbin Airport.”

The investigation found that when control of the aircraft was lost, there was insufficient height to recover.

“Having a clear, defined emergency plan prior to the critical stages of the flight removes indecision and reduces pressure on the pilot while in a high-stress situation,” Mr Macleod said.

“Proficiency in in-flight emergencies can be improved by regularly practicing these emergencies. Additionally, flying the approach as per manufacturer and airport procedures places the aircraft in the optimum configuration and position.”

Mr Macleod noted that the ATSB publication Managing partial power loss after take-off in single-engine aircraft provides guidance that is also applicable to an engine failure occurring at low-level during an approach.

“Taking positive action and ensuring that control is maintained has a much better survivability potential than when control of the aircraft is lost,” he said. “In addition, using the aircraft structure and surroundings to absorb energy and decelerate the aircraft can assist in minimising injury.”

The investigation examined the aircraft’s engine and fuel system, and did not identify any failures or issues that may have contributed to the loss of engine power.

Read the final report: Loss of control and collision with terrain involving Cessna 172, VH-EWE, near Moorabbin Airport, Victoria, on 8 June 2018


Fuel drum contamination

The origin of a white, rubbery contaminant discovered in Jet A1 fuel drums was determined to be sealant used on drum lids and bases, an ATSB investigation has found.

In September of 2016, the ATSB received a report from a helicopter operator in Cloncurry, Queensland, that while inspecting one of several recently arrived drums, a pilot had discovered white particles floating in the Jet A1 fuel. The same material, described as small pieces of white debris that tended to settle at the base of the drum, was subsequently found in all seven of the drums that were opened and inspected.

The same operator would subsequently report further instances of fuel drum contaminants, from a second location in Queensland and two remote sites in Western Australia on separate occasions in 2016, 2017 and 2019.  

The operator advised that the contaminated drums had been filled by different refuelling companies but all had been manufactured the same company, VIP Packaging. Batch numbers and manufacturing dates on the drums across the incidents did not show any correlation.

There are a number of ways to minimize the likelihood of using contaminated fuel.

The ATSB determined that the contaminant was a sealant used by the drum manufacturer on the lid and base of the drums. The sealant’s mechanical properties were found to degrade when exposed to Jet A1 fuel. This, in combination with vibration and drum deformation during transport to remote locations over rough roads, likely resulted in pieces of sealant entering the fuel within the drum.

“Fuel sourced from drum stock is particularly susceptible to contamination. However, there are a number of ways to minimise the likelihood of using contaminated fuel,” ATSB Director Transport Safety Stuart Macleod said.

“These include applying appropriate drum handling and storage methods; visually inspecting drums for contaminants prior to refuelling activities; regularly inspecting fuel pump filters; and conducting fuel drains from the aircraft after each refuel for visual inspection.”

Mr Macleod noted that the investigation established that no contaminants were found in any aircraft exposed to the fuel.

“Filtration during the refuelling process appears to be effective in preventing these contaminants from reaching the aircraft and there was no evidence that the sealant dissolved in the fuel.”

The report notes it is possible that the sealant may break down into small enough pieces to pass through a fuel transfer pump’s micronic pre-filter and reach the aircraft’s fuel tank, and from there pass through the aircraft’s fuel filtration system and enter the engine.

“However, if that was to occur, the particles would be in minor quantities and too small to affect engine operation,” Mr Macleod said.

“As long as fuel is filtered as required under the regulations, and in accordance with best practice, harmful contaminants should not be able to reach the aircraft.”

Read the final report: Drum stock fuel contamination, Cloncurry Airport, Queensland, on 7 September 2016

New safety measures

A signal maintenance mechanic working on crossover points at Clyde rail yard, western Sydney, entered the danger zone before being struck by a passenger train and sustaining fatal injuries in the early morning of 18 June 2016.

A transport safety investigation into the accident, conducted on behalf of the Australian Transport Safety Bureau by NSW’s Office of Transport Safety Investigation (OTSI), determined that two signal maintenance team workers (a mechanic and an electrician) had assumed their worksite was within the protective limits of a Track Occupancy Authority (TOA) established for a civil maintenance team tasked to replace sleepers under the crossover at 64 points.

However, the protective limits of the TOA extended only to defined clearance points on either side of 64 points and did not include the 63B points, on the Up main line, where the signal maintenance team entered the danger zone.

The accident highlights the importance of planning and integrating safety across the entire scope of work.

“The investigation found that Sydney Train’s work-planning process, involving multiple work groups, did not assure the consideration of worksite safety for all tasks undertaken by each party over the duration of the work and when returning the rail infrastructure into service,” said OTSI Deputy Chief Executive Officer Kevin Kitchen.

The civil maintenance team’s Protection Officer (PO) was aware of the signal team’s work tasks but did not consider these in his worksite protection arrangements. The PO had not been briefed on the scope of the signal team’s work, and so did not provide protection at 63 points.

The investigation also identified that the network communications by various parties in Sydney Trains were not in accordance with the principles underpinning the network rules.

“This accident highlights the importance of planning and integrating safety across the entire scope of work,” said Mr Kitchen. “It also highlights the importance of briefing all workers, and of all workers seeking a safety briefing about the worksite protection plans before work commences and when circumstances change.”

Following the accident, Sydney Trains implemented a number of safety actions and delivered on safety commitments. These included requiring proposed worksite protection plans be reviewed and validated by Sydney Trains’ Corridor Safety Centre; appointing additional rail safety coaches and mentors, with a required coaching session for all Protection Officers at least once per year; and requiring Protection Officers implement a form of worksite protection at least once every quarter to remain eligible to be re-certified as a Protection Officer.

Additionally, Sydney Trains established a Post-Incident Assurance Group to respond to the accident. This Group established key focus areas to promote the safety of workers and avoid future incidents. These areas included worksite protection, culture, planning for maintenance work, and safety-critical communications.

The Group later established the Safety Focus Program, whose initiatives include safety focus sessions, a safety culture program, improvements to protection officer selection and training, a signal key switch project, safety-critical communication enterprise-wide program, and a maintenance access planning project.

Read the final report: Track worker fatally injured when struck by train W510, Clyde, New South Wales, on 18 June 2016

HUET contributes to survivability

A helicopter crew has credited their surviving a collision with water with skills learned and practised as part of Helicopter Underwater Escape Training (HUET).

The 28 January 2019 accident occurred when Sikorsky S-64E Skycrane helicopter, registration N173AC, was conducting firebombing operations to the west of Thomson Dam in Victoria’s Yarra Ranges National Park. All three crewmembers were highly experienced, and twice during the day, they had utilised the nearby Wood Creek Dam to fill the helicopter’s tank using its pond snorkel.

On the day’s third visit to Wood Creek Dam, while descending with a nose-high attitude, the helicopter’s tail struck the water, which then submerged and resulted in the tail rotor detaching. The helicopter then rotated rapidly, its main rotor blades separated as they contacted water, the right cockpit door separated from the fuselage, and the helicopter came to rest on its left side, submerging the cockpit.

The crew would recall that it was not possible to see anything underwater, and that jet fuel contamination was present. Each recalled the rehearsed drills from their helicopter underwater escape training, and they identified their harnesses and nearest exit to orientate themselves in the aircraft. They all waited until the last moment to draw a breath, and did not unbuckle and attempt to exit the helicopter until motion had ceased.

One crewmember sustained a knee injury while the other two were uninjured. All three crew successfully exited the aircraft, inflated their life jackets, and swam to shore. The aircraft was substantially damaged.

Helicopters excel in confined areas, but are vulnerable when operating within them.

“The ATSB has previously emphasised the importance of helicopter underwater escape training,” ATSB Director Transport Safety Stuart Macleod said. “Indeed, in the wake of a separate, sadly fatal, accident the ATSB released a Safety Advisory Notice highlighting the importance of HUET regular training. This accident demonstrates the value of that training in saving lives.”

Mr Macleod noted that accident highlighted another survivability consideration, as neither pilot unplugged their helmet. However, the extension cords from the aircraft to the helmet plug allowed the plug to release, preventing the helmets from snaring them.

“Following an accident, it is common for air crew to overlook the need to unplug their helmet,” he said. “Using a good quality extension cable that will maintain the integrity of communications and release under tension in the event of an emergency can also save lives.”

The ATSB investigation into the accident established that, over the course of the day’s operation, the helicopter’s approach path to the dam was incrementally shortened. The length of the final approach was considerably shorter than earlier approaches.

ATSB investigators determined that it was likely that the final tight approach path was at the upper margins of allowable speed and angle of bank. This would have required a steep flare on arrival and likely resulted in the rapid onset of vortex ring* state.

“When performing aerial work, it is easy to accept incremental changes that gradually reduce margins. While these changes often increase efficiency, it is worth checking how much a sequence has deviated from earlier versions and re-evaluating elements if they appear less stable,” Mr Macleod said.

“Helicopters excel in confined areas, but are vulnerable when operating within them. In this case, the shape of the dam and surrounds of the site reduced the opportunity for recovery. Periodic reassessment of confined areas, and approach and departure profiles should be done throughout the duration of an operation.” 

*Vortex ring state occurs when a helicopter descends into its downwash, where air recirculates back up and over the rotors instead of flowing down and away. This causes the same parcel of air to circulate around the rotor. As a result, the rotor system no longer has the steady stream of air required to produce lift and the helicopter will descend despite the application of additional power.

Read the final report: Collision with water involving a Sikorsky S-64E Skycrane helicopter, N173AC, near Jericho, Victoria, on 28 January 2019

High rate of descent

An AW139 helicopter experienced an uncommanded high rate of descent during a search for a recreational fishing vessel while the crew was flying with the aid of night vision goggles in bushfire-affected low visibility conditions at night.

An ATSB investigation into the 13 May 2018 incident found the pilot, who was flying under night visual flight rules, lost visual cues while descending to 400 feet above ground level to confirm the potential source of a transmitting EPIRB beacon, in the vicinity of Salt Water Arm, approximately 40 km east of Darwin. The pilot’s intent was to decrease rate of descent and airspeed before activating the helicopter autopilot’s auto-hover (HOV) mode at 400 ft above ground level (AGL), however at the point of ‘HOV’ mode activation, the AW139 was descending at over 1,300 feet per minute.

The aircrew officer, who was also using night vision goggles and was monitoring the descent from the helicopter’s main cabin, alerted the pilot over the intercom of the high rate of descent, before calling ‘Climb! Climb! Climb!’

The crew’s use of standard patter and practiced drills allowed them to recover the situation and avert an accident.

By this point the pilot had clear visual cues and also detected the rapid rate of closure with the ground, and instituted a recovery in accordance with drilled emergency procedures, overriding aircraft automatics and using forward cyclic and collective to reverse the rate of descent.

The aircraft descended to a height of 31 feet AGL before attaining a positive rate of climb. Occupied with flying the recovery procedure – flying solely through the outside picture and the attitude indicator – the pilot did not observe a main transmission torque limit exceedance message.

The helicopter safely recovered to Darwin, and subsequently returned to the Salt Water Arm area on a second flight to conduct a successful search for the source of the EPRIB transmission, found to be a small recreational fishing boat.

Describing the effect of smoke on pilots, ATSB Director Transport Safety Stuart Macleod said “During the approach to hover in a degraded visual environment, searching outside for visual cues drew the pilot’s attention away from the flight instruments. This resulted in flight instruments not being referenced when they were needed.

“With the aircrew officer in the helicopter’s main cabin, in anticipation of having to operate the winch, rather than next to the pilot in the cockpit, this negated the benefit of having a trained and competent crewmember to assist the pilot, resulting in a degraded monitoring capability in the approach to hover.”

Application of good crew resource management and practiced recovery techniques supported the crew in restoring control, Mr Macleod noted.

“The crew’s use of standard patter and practiced drills allowed them to recover the situation and avert an accident.”

When on the ground at Darwin, the crew could not confirm indications of the main gearbox overtorque exceedance, and a maintenance message was not detected on the crew alert system, which displays messages regarding the operation and condition of the aircraft for crew information and action. As a result, the helicopter was flown on the second sortie that evening, despite the overtorque exceedance requiring the AW139 to be grounded until the engine and airframe manufacturers could assess the helicopter as serviceable.

In reference to the uncommanded high rate of descent, Mr Macleod said the incident underlines the need for pilots to be aware of the human factors hazards associated with a loss of visual references.

“Pilots can protect themselves by maintaining the use of instrument scans in approaches at night, and making use of monitoring by trained and available crewmembers,” he said. “Instrument flight rules (IFR) pilots in IFR-rated aircraft should prioritise the use of inadvertent instrument meteorological conditions drills and pre-planned exit routes over recovery of visual meteorological conditions.”

The investigation also highlighted that flight crew and engineering teams should not rely solely on indicators, or the absence of indicators, to determine airworthiness.

“If there is any reason to suspect that aircraft limits have been exceeded, operators should run diagnostics to determine the airworthiness of the aircraft beyond doubt,” Mr Macleod said.

Since the incident the helicopter’s operator, CareFlight, introduced three new risk controls to prevent a similar occurrence, including updating standard operating procedures with stabilised approach criteria to require an immediate go-around if the aircraft leaves a prescribed range of parameters, and improved auto hover functions advice. In addition, the ground-based training syllabus now incorporates controlled flight into terrain avoidance training.

The investigation also noted that the EPIRB was not registered to its current owner and was incorrectly placed in the boat, causing the beacon’s signal to be scattered and leading to a loss of accuracy in the helicopter’s direction-finding equipment. As a result, the mission’s complexity and time taken to rescue were increased.

Read the final report: Loss of control in flight involving Leonardo Helicopters AW139, VH-YHF, near Adelaide River mouth, 38 km east-north-east of Darwin, Northern Territory, on 13 May 2018

Track obstruction risks

A passenger train sustained minor damage after colliding with a metal awning from a modified shipping container that was being transported by a freight train, which had opened in transit before striking a bridge and falling onto the track.

The 20 foot container, modified with a large side opening awning for use as a canteen, was travelling on Pacific National train 7WB3 from Newcastle to Brisbane on 17 June 2018. As the container passed over Wilson River Bridge, near Telegraph Point in NSW, the open awning struck the bridge superstructure and fell onto the track.

The ATSB investigation into the incident established that the awning had opened twice previously during transit. On both those occasions the crew re-secured the awning, but they were unaware of the third opening before the awning struck the bridge.

Train 7WB3 then continued north and stopped in the Telegraph Point passing loop to allow southbound passenger train NT32 to pass on the mainline. As NT32 crossed south over the Wilson River Bridge, it struck the awning and sustained minor damage to brake equipment on the train’s leading bogie.

The ATSB found that the awning was only held closed by spring-loaded bolts accessed from the inside of the container. This was not compliant with Pacific National’s Freight Loading Manual (FLM), which required a system that could be locked and was externally visible to assure that openings remained secure and enable examination by inspection staff. Further, inspections conducted by Pacific National terminal operators at the departure location did not identify the modified container or the absence of locks.

Any item on a container that can open into the rail corridor represents a potential risk as, should they come open, they may strike infrastructure, opposing trains or bystanders.

“The absence of externally visible locks meant there was no way of knowing whether the modified container’s awning was adequately secured,” ATSB Transport Safety Director Dr Stuart Godley said.

“Should any opening come open during operation, they may strike infrastructure, opposing trains or bystanders.”

The ATSB also noted that, while Pacific National made the FLM available to customers, they did not actively advise them when they had a responsibility identified by the manual and did not have a process for ensuring customers complied with the manual’s requirements. Therefore, in this case, the customer did not notify Pacific National that the container was modified as they were not aware of a requirement to do so. Additionally, the training and checking processes for terminal operators who carried out inspections did not include the FLM requirements for modified containers. This removed an opportunity for the requirements to be reinforced and practiced during training and regular checking of inspection staff.

“This incident highlights the importance of having processes in place to advise customers of the requirements for the safe transport of modified containers and to ensure compliance,” Dr Godley said

Since the incident, Pacific National has implemented a range of processes to ensure customers are aware of, and are compliant with their FLM requirements. This has included the development of an online course and an auditing program to monitor compliance and performance.

In addition, Pacific National have also introduced a number of training and checking measures for inspection staff.

Read the final report: Track obstruction due to loss of freight from train 7WB3 and subsequent impact of passenger train NT32 with track obstruction, near Telegraph Point, New South Wales, on 17 June 2018

Landing gear wheel failure

After a wheel on one of its Boeing 737s failed, Virgin Australia implemented new landing gear wheel inspection requirements, while the wheel manufacturer, Safran, updated the relevant component maintenance manual.

The wheel failure event occurred on 4 January 2017 when the 737-800 was holding on taxiway Brisbane Airport B3 when the crew heard a loud noise they thought was a burst tyre. The crew attempted to taxi back to the gate, but were held short when an engineer observed that the left main landing gear main wheel assembly had failed.

The flight was cancelled and passengers disembarked, however the aircraft could not be jacked and towed via the axle due to the damaged wheel. Instead, wing jacks were used to allow a double wheel change on the tarmac. The aircraft was then towed to a maintenance facility for examination.

…There were no mandated inspections suitable for detecting such loosening.

An ATSB investigation found that the wheel had ruptured due to tie bolt assemblies having loosened while in service. This allowed the two wheel halves to move relative to each other, resulting in a fatigue crack and eventual wheel rupture. The loosening was most likely due to the presence of anti-seize compound between the wheel halves, which affected the clamping forces.    

“This incident highlights the importance of compliance with all aspects of manufacturers’ maintenance procedures, including the appropriate application of anti‑seize,” said ATSB Director Transport Safety Stuart Macleod. “This is especially important if, as in this case, there is no simple means of detecting the effect that such excess product can have on fastener security.”

The ATSB found that while the bolt assemblies on this single-web wheel-type were more prone to in-service loosening than dual-web wheels, there were no mandated inspections suitable for detecting such loosening. There were also no mandated risk controls to prevent loosening or subsequent rupture.

Virgin has advised that in response to this incident, it has implemented regular inspections to identify and prevent the loosening of tie bolt assemblies. Safran, the wheel manufacturer, updated the wheel’s component maintenance manual with more detailed instructions for applying anti-seize compound.

Finally, Boeing advised 737 NG operators of two possible courses of action to address the issue of potential wheel failures based on two optional service bulletins that it had in place prior to the occurrence.

The particular wheel type was installed on approximately 2,000 737 NG aircraft in service worldwide. Boeing has delivered approximately 7,000 737 NG aircraft in total.

Read the final report: Main landing gear wheel failure during taxi involving Boeing 737, VH-VUH, at Brisbane Airport, Queensland, on 4 January 2017

Accident highlights hypoxia risk

The pilot of a Cessna Grand Caravan was almost certainly incapacitated, possibly from hypoxia, when his aircraft flew uncontrolled into the ocean off the east coast of Japan.   

The Australian-registered Cessna 208B (VH-FAY) was being ferried from Perth to Mississippi in the United States via the Northern Pacific when on the morning of 27 September 2018 it departed from Saipan Airport in the Northern Mariana Islands bound for New Chitose Airport in Hokkaido, Japan.

After climbing for about an hour, the aircraft levelled off at 22,000 feet, while after 2 hours and 20 minutes into the flight, the pilot contacted Tokyo Radio flight information service on HF radio to make a mandatory position report. The aircraft was next due to report about an hour and 20 minutes later, when overhead the SAGOP reporting point, but no contact with Tokyo Radio was made. Tokyo Radio subsequently made repeated attempts to communicate with the pilot, without success.

About 4.5 hours after the pilot’s last communication, two Japan Air Self-Defense Force (JASDF) aircraft intercepted the Cessna. The pilot did not respond to the intercept in accordance with international intercept protocols, either by rocking the aircraft wings or turning, and the aircraft continued to track at 22,000 feet on its planned flight route. The JASDF pilots were unable to see into the cockpit to determine whether the pilot was in his seat or whether there was any indication that he was incapacitated.

After about 30 minutes, the JASDF pilots observed the aircraft descend into cloud. The aircraft descended rapidly and disappeared from radar less than 2 minutes later. Within 2 hours, search and rescue personnel located the aircraft’s rear passenger door. No other aircraft parts were located and the pilot was not found.

Rear passenger door

Figure 3: Rear passenger door.
Source: Aircraft operator

Source: Aircraft operator

The ATSB’s subsequent investigation found that while the aircraft was in the cruise on autopilot, the pilot almost certainly became incapacitated. Consequently, about 5 hours after the last position report, without pilot intervention to change fuel tanks, the aircraft’s engine stopped, likely due to fuel starvation. This resulted in the aircraft entering an uncontrolled descent into the ocean.

The effects of hypoxia can be insidious.

Director Transport Safety Stuart Macleod said that while the cause of the incapacitation could not be determined, and a medical event could not be ruled out, the pilot was operating alone in an unpressurised aircraft at 22,000 feet and probably using an unsuitable oxygen system, which increased the risk of experiencing hypoxia.

“Operating unpressurised aircraft above 10,000 feet requires careful oxygen management and planning,” Mr Macleod said.

“Where an increased risk of hypoxia exists, good risk management practices should be used for flight planning. Because the effects of hypoxia can be insidious, training in recognition of early symptoms of hypoxia can increase the time available to react, descend and resolve any issues.”

As a result of this accident, the aircraft operator amended its operation manual to include additional guidance for international ferry flights. It also created an oxygen-use guide and a specific risk assessment for positioning (ferry) flights.

Read the report: Collision with water involving Cessna 208B, VH-FAY, 185 km north-east of Tokyo, Japan, on 27 September 2018

Bogie fatigue cracking

A fatigue crack in a coal train wagon bogie went undetected during preventative maintenance before it escalated to a full fracture, increasing the risk of derailment, an ATSB investigation has highlighted.

On 12 December 2017 Pacific National coal train TM78A was undergoing a roll-by inspection at Kooragang Coal  Terminal in Kooragang, New South Wales, when a maintenance worker identified a fracture on the lead bogie of the train’s 35th wagon. The train was stopped and the wagon was removed for inspection.

An investigation into the cracking, conducted on behalf of the ATSB by NSW’s Office of Transport Safety Investigation (OTSI), found that the fatigue crack had gone undetected during earlier preventative maintenance, and that it was probable that the fracture was visible the day before during unloading of the wagon, but had gone undetected.

Identifying this fracture in time likely prevented a derailment.

The NDCA bogie frame design has a history of fatigue cracking, which increases the risk of derailment if the cracking is not identified. Pacific National had processes in place to identify fatigue cracking, but this crack was likely not detected due to the location of the defect on the bogie frame.

OTSI COO and Deputy Chief Investigator Kevin Kitchen said the incident highlights how asset managers should ensure that inspection techniques effectively monitor and report on the condition of assets.

“Risk controls should also be continuously assessed to control risk to an acceptable level through the life cycle of an asset,” Mr Kitchen said.

In response to the incident, Pacific National has made changes to the maintenance standard used during scheduled maintenance, increasing the area of the bogie frame subjected to non-destructive testing. This change is aimed at identifying and addressing fatigue cracking prior to any escalation of defects.

“Identifying this fracture in time likely prevented a derailment,” Mr Kitchen said. “However, if the worker who identified the defect had been positioned on the opposite side of the train, it could have been missed.”

Read the final report: Fractured bogie frame on coal train TM78A, at Kooragang, New South Wales, on 12 December 2017

Fatigue crack engine failure

A fatigue crack in a turbine blade spread rapidly, causing a helicopter’s engine failure, an ATSB investigation found.   

The incident occurred when a twin-engined Airbus Helicopters AS355F-1 helicopter, registered VH-SEV, was completing an air-taxi from a hangar to a maintenance facility at Sydney’s Bankstown Airport. On board were the pilot and one passenger.

As the skids touched the ground on landing, the pilot heard a loud ‘squeal’ from the helicopter’s right-hand side. The pilot scanned the instrument panel and observed the engine gas generator speed (Ng) drop to 55 per cent and the right-hand engine chip light illuminate. A few seconds later, the pilot observed smoke coming from that side of the aircraft and immediately shut down the right-hand engine.

Mechanics from a nearby workshop quickly extinguished the engine fire. There was substantial damage to the engine, and minor heat damage to the surrounding structure of the helicopter.

Any pilot, regardless of their level of experience, can find themselves confronted with an unexpected failure.

“Any pilot, regardless of their level of experience, can find themselves confronted with an unexpected failure,” said ATSB Director Transport Safety Stuart Macleod. “The pilot’s quick response to the unexpected failure helped ensure the best possible safety outcome.”

The ATSB investigation found that single third-stage turbine wheel blade failed due to fatigue cracking, resulting in secondary damage to the engine, and total engine failure.

“This incident reinforces that it is important for pilots to monitor aircraft performance parameters continuously for abnormal indications,” said Mr Macleod.

Engine manufacturer Rolls-Royce advised the ATSB that, with the Rolls-Royce 250 enhanced power turbine engine, a dwell of just a few seconds can be enough to initiate damage and propagate a crack to failure.

In response, Rolls-Royce is redesigning the third-stage turbine wheel to improve its tolerance to fatigue cracking and operation at responsive wheel modes.

The report AO-2018-021, provides important advice for operators of aircraft with Rolls-Royce 250 enhanced power turbine engines.

Read the final report: Engine failure involving an Airbus Helicopters AS355F-1, VH-SEV, Bankstown Airport, New South Wales, on 12 March 2018