Loss of visual reference

Key points:

  • Cloud and low visibility almost certainly precluded the pilot from navigating by ground reference
  • The aircraft collided with terrain in level flight, under power
  • ATSB remains concerned about the frequency of accidents, many fatal, which involve pilots flying with reduced visual cues

Low cloud and reduced visibility almost certainly resulted in the pilot of a Cessna 182 losing visual reference with the ground before the aircraft collided with rising terrain.

The aircraft had departed Mount Garnet, far north Queensland for a 20-minute flight under visual flight rules (VFR) to Atherton, with the pilot the sole occupant. The forecast weather for the 8 April 2019 flight included low cloud extending to the ground in areas of higher terrain, and low visibility in cloud and showers of rain.

The ATSB’s investigation into the accident found that cloud and low visibility almost certainly precluded the pilot from navigating by ground reference, and changes in aircraft direction and altitude, as recorded by the aircraft’s GPS unit, were indicative of the pilot manually flying the aeroplane rather than having the autopilot engaged.

“Changes in track were consistent with what would be expected if attempting to avoid weather,” said ATSB Director Transport Safety Dr Stuart Godley.

As the aircraft approached the Herberton Range it climbed to an altitude about 400 feet higher than the highest terrain in the area, but this was very likely not above the cloud tops, the investigation notes. It could not be known whether the pilot then descended in an attempt to get under the cloud, having lost visual reference with the ground, or due to geographical disorientation, having assessed the aircraft was beyond the range and closer to Atherton.

“Low cloud and reduced visibility obscured rising terrain, and this almost certainly resulted in the pilot losing visual reference with the ground and the aircraft colliding with terrain in level flight, and under power and pilot control.”

The aircraft impacted the tree canopy and terrain, and the pilot sustained fatal injuries. The 130 metre-long wreckage trail was consistent with significant forward speed at impact. No pilot radio calls were recorded.

“This tragic accident highlights that any pilot, no matter their level of experience, is at risk of experiencing disorientation and a loss of spatial awareness due to reduced visual cues if pressing on into instrument meteorological conditions (IMC) without a current instrument rating and in a suitably-equipped aircraft,” said Dr Godley.

Accidents involving visual flight rules pilots in Instrument Meteorological Conditions

The ATSB remains concerned about the frequency of accidents which involve pilots flying with reduced visual cues, as highlighted by its ‘Don’t push it, DON’T GO' – know your limits before flight’ safety campaign.

“The risks associated with operating under visual flight rules in adverse weather should not be under-estimated,” Dr Godley said.

“Understanding weather-related hazards and how to assess and mitigate them are vital skills for pilots, particularly those who fly in challenging environments like mountainous terrain.

“During flight, it is critical that pilots continuously assess the weather, and if conditions deteriorate make timely decisions to turn back, divert or hold in an area of good weather. Don’t push it, don’t go. Know your limits before taking off.”

The ATSB continues to encourage VFR pilots to use a ‘personal minimums’ checklist to help control and manage flight risks through identifying risk factors that include marginal weather conditions, and only fly in environments that do not exceed their capabilities.

“As a personal ‘go/no-go’ checklist they can help take the stress out of difficult decisions both before and during flight, and act as a safety buffer between the demands of the situation and the extent of a pilot’s skill,” Dr Godley said.

Short case studies of ATSB investigations into accidents involving VFR pilots encountering IMC are published in the ATSB’s recently-updated Accidents involving pilots in Instrument Meteorological Conditions publication.

“Weather-related general aviation accidents remain one of the ATSB’s most significant causes for concern in aviation safety,” Dr Godley said.

“The ATSB encourages VFR pilots to learn from the experiences of others, to help build a robust understanding of the risks of flying into IMC and just how rapidly such accidents can happen.”

Read the final report: Controlled flight into terrain involving Cessna 182, VH-DJN, 14 km south-south-west of Atherton Airport, Queensland, on 8 April 2019

Read the Accidents involving Visual Flight Rules pilots in Instrument Meteorological Conditions publication.


Uncommanded engine shutdown

Key points:

  • Uncommanded engine shutdown due to bearing fracture
  • On the day before the flight, metal debris was detected on the engine chip detector
  • Crew were unable to feather the propeller and it continued to rotate at low speed, in a coarse pitch condition

Confusing and ambiguous procedures probably led to maintenance personnel releasing to service a DHC-8 (Dash 8) aircraft which subsequently experienced an uncommanded in-flight engine shut down after metal debris had been detected on the engine’s chip detector, a new ATSB report details.

The QantasLink-operated DHC-8-400’s right engine, a Pratt & Whitney Canada PW150A, shut down uncommanded as the aircraft approached the top of the descent north of Brisbane Airport when operating a scheduled passenger flight from Mackay on 26 June 2018. The crew actioned the engine shutdown checklist but the propeller did not feather and continued to rotate at low speed in a coarse pitch position. The crew actioned the ‘Non-Normal’ checklist and continued to Brisbane for a safe landing.

“Examination of the affected engine at Pratt & Whitney’s facility in Canada found that the uncommanded shutdown occurred as a result of a bearing fracture in the tower shaft for the accessory gearbox that runs the main engine oil pump and fuel-metering unit,” ATSB Director Transport Safety Mr Stuart Macleod said.

However, consistent with previous similar occurrences, due to the extent of the damage it was not possible to establish the cause of the bearing fracture, the ATSB investigation notes.

Mr Macleod said the investigation found that maintainers missed an opportunity to ground the aircraft when, on the day before the flight, metal debris was detected on the engine’s chip detector.

“Procedures in the aircraft maintenance manual were confusing and ambiguous and this probably led to a misunderstanding which allowed the aircraft to be released to service.”

The investigation found that following the detection of debris on the chip detector and the oil filter, maintenance personnel discussed a previous detection of debris but incorrectly concluded that it did not need to be considered. This resulted in the aircraft being released to service with a 20 flight-hour limitation.

In response to the incident Pratt & Whitney Canada have standardised the wording relating to debris analysis guidance in the aircraft maintenance manual.

“The ATSB acknowledges the improvement this will make, but still considers there is ambiguity and the potential for confusion in the procedure and has asked Pratt & Whitney to take further action to improve the clarity of the chip detector debris analysis section of the manual,” Mr Macleod said.

In addition, QantasLink have introduced a system to monitor metallic debris found on chip detectors to assist in trend identification, and have issued an airworthiness standing order to all certifiers within the approved maintenance organisation to introduce a single certification statement standard for all maintenance.

“Clear and unambiguous procedures are very important to avoid misinterpretation and error when performing safety‑critical tasks like aircraft maintenance,” Mr Macleod said.

“This occurrence also illustrates that the high reliability of modern aircraft maintenance depends on accurate record keeping of all performed tasks to both communicate what has been done and assist in trend identification.”

QantasLink have also issued a technical advisory bulletin to DHC-8-400 pilots advising them of the incident and warning that propellers may not always feather as practiced in the simulator.

Despite detailed technical examination, the reason the propeller did not feather could not be established.

However, the propeller did go to a ‘safe coarse’ condition due to the counterweights in the propeller system, as it would if there was no oil in the propeller system, and QantasLink identified that the one engine inoperative performance reduction between a counter‑weight coarsened propeller and a fully feathered propeller was only 0.5–0.9 per cent.

Read the final report: Uncommanded engine shutdown involving De Havilland Aircraft of Canada DHC-8, VH-LQD, 77 km north-north-west of Brisbane Airport, Queensland, on 26 June 2018

Thunderstorm-related turbulence

Key points:

  • The primary protection against thunderstorm-related turbulence is avoidance
  • 10 nautical miles was not enough separation to ensure safe passage from a thunderstorm
  • Incident occurred two years after two pilots were fatally injured in an in-flight breakup of another Cessna 210, which had encountered severe turbulence

Despite attempting to avoid a thunderstorm while flying in the Top End during the build-up, the pilot of a single-engine Cessna encountered sudden and sustained severe turbulence, resulting in a loss of control for an extended period and minor injuries to passengers.

The Cessna 210M, registered VH-SJW and operated by Mistar Holdings, was conducting a passenger charter flight with a pilot and four passengers on board from Darwin to Tindal, Northern Territory, on 25 November 2019. Soon after departure, the pilot diverted five nautical miles right of the planned track to avoid a large storm cell that was five nautical miles left of track.

While maintaining 3,500 feet, the aircraft encountered sudden and sustained severe turbulence. Control of the aircraft was lost for over three minutes, with the pilot having no control over bank angle, height or heading for extended periods. Radar at Darwin recorded the aircraft’s highest groundspeed as 210 knots, and rate of descent at one point to be 5,000 feet per minute with a lowest altitude of 1,200 feet.

Three of the passengers sustained minor injuries.

After landing safely at Tindal, the pilot inspected the Cessna for potential damage, before flying the aircraft for over an hour to Millingimbi to pick up four more passengers for a charter flight to Galiwin’ku (Elcho Island).

That evening, the pilot reported the incident to the operator who, upon receiving notification of the turbulence encounter, grounded the aircraft at Galiwin’ku, pending an engineering inspection.

This serious incident occurred just seven months after the ATSB published the final report from its investigation into the in-flight break up of another Cessna 210, which claimed the lives of two young pilots on 23 October 2017. The pilots had encountered severe turbulence while attempting to avoid thunderstorm activity to the east of Darwin during a flight to Galiwin’ku.

That investigation found a combination of airspeed, turbulence and control inputs probably led to excessive loading on the aircraft’s wings, which separated from the fuselage in-flight.

“These two investigations highlight the importance of recognising and avoiding tropical weather conditions that present significant hazards to flight,” ATSB Director Transport Safety Dr Mike Walker said.

“Identifying an appropriate distance to keep from thunderstorms, which comes through experience in operating in the tropics, can be particularly challenging for pilots.

“In many cases, deviations of 10 nautical miles may not be enough for an aircraft to remain safely clear of the turbulent and powerful forces associated with storms.”

The ATSB’s investigation into the 2019 occurrence also found that the operator did not have guidance to direct pilots to seek advice or peer support following abnormal events.

“Following the turbulence encounter, the inspection carried out by the pilot was not sufficient to ensure the airworthiness of the aircraft beyond doubt,” Dr Walker said.

“Flying another charter flight without an inspection by a qualified maintenance engineer exposed the operator, the pilot and the passengers to elevated risk.”

The investigation also highlights that the primary protection against thunderstorm related turbulence is avoidance, Dr Walker said.

“Operators, pilots and passengers can work together to avoid flying in adverse weather. For instance, by starting a day’s flying early it can be completed before weather becomes a problem typically in the afternoon.”

The investigation report notes that a pilot with the best intentions may make a suboptimal decision after experiencing an abnormal event.

“Operators can provide guidance to assist pilots to make good decisions in these situations, by providing peer support and emphasising the importance of reporting abnormal events in a timely manner,” Dr Walker said.

“Early reporting reduces pressure in operations, allowing ample time to make alternative arrangements.”

In October 2019, an ATSB Senior Transport Safety Investigator joined Aviation Safety Advisers from the Civil Aviation Safety Authority (CASA) in Darwin and Cairns to discuss with local pilots how to make more informed and rational decisions when managing the hazards associated with flying across the Top End during the build-up and wet seasons.

Later this evening [15 September 2020], CASA and the Bureau of Meteorology are holding a safety seminar in Darwin to again highlight the dangers of flying near thunderstorms for both general aviation and commercial pilots.

“Pilots should regularly review operational documents and industry advice to build on their experience and to develop a comprehensive understanding of the challenges of flying in the Top End, and the strategies available to reduce risk,” Dr Walker said.

Following this serious incident, the operator developed case studies for pilots, emphasising weather avoidance and management of abnormal events. These have been integrated into proficiency checks to ensure solid understanding of theory, and practical application of weather avoidance, escape and post encounter management.

Read the final report: Severe turbulence and loss of control involving a Cessna 210M, VH-SJW, 30 km south of Darwin Airport, Northern Territory, on 25 November 2019

Bulk carrier grounding

Key points:

  • Electrical power lost when the auxiliary generators shut down due to overheating cooling water
  • Blackout resulted in a loss of propulsion and steering control
  • Bridge communications were ineffective and the pilots were not informed of the machinery problems prior to the blackout

A bulk carrier ran aground in a channel during its departure from Dampier, Western Australia when it lost steering and propulsion due to a total electrical blackout from a failed generator.

The ATSB investigation into the 11 March 2018 grounding found that the 298 metre, Panamanian-flagged Bulk India had lost all steering control and propulsion when shortly after the main engine was increased to full ahead, the ship’s auxiliary diesel generator engines shut down after the cooling water temperature controller failed, resulting in overheated cooling water.  

In addition, when the ship’s emergency generator started in response to the blackout, it also shut down from overheating as a radiator fan belt that had failed several months earlier had not been replaced.

As a result, control of the Bulk India, which at the time had one tug in attendance and two pilots on-board, was lost and the rudder remained fixed at 20° to port. The ship turned to port and contacted the channel side, running aground.

The ship was recovered into the channel with the aid of tugs, before being taken out the channel to anchor. A subsequent dive inspection of the hull found evidence of contact with the bottom but no significant damage.

“The ATSB investigation found that the ship’s engineers did not immediately identify the problem and were unable to manually operate the cooling water temperature control valve in time to prevent the blackout,” said ATSB Director Transport Safety Mr Stuart Macleod.

“The investigation also found that while the problems in the engine room started about 13 minutes before the blackout, the two pilots on board were not informed of the situation. This removed the opportunity for the pilots to prepare for the loss of control, and delayed actions that may have assisted in a more timely or more effective response.”

The ship operator’s lack of adequate procedures to ensure that critical spares were identified and maintained in inventory to guarantee availability when required on board also contributed to the grounding, the investigation notes.

“This investigation highlights that ship operators and crewmembers should ensure that systems, machinery and equipment critical to the continued safe operation of the ship are thoroughly understood, as well as appropriately maintained and tested,” said Mr Macleod.

Subsequent to the grounding, the ship’s operator made improvement to their safety management and operating systems, as well as staff education and training processes.

Separately, Rio Tinto have revised escort towage arrangements for ships departing their facilities in Dampier following extensive simulation exercises and a review of existing risk assessments. As a result, a second tug remains in attendance with bulk carriers for further along the channel. Further, a comprehensive guidance manual for ship towage operations in Dampier and Port Walcott was developed.

Read the final report: Grounding of bulk carrier Bulk India, Dampier, Western Australia, on 11 March 2018

Undetected fatigue failure

Key points:

  • Pedal breaks, jams following small control input
  • Failure likely due to a pre-existing fatigue crack, undetected at previous 100-hourly inspection
  • Maintenance organisation to conduct magnetic particle inspection of pedal assembly at 2,200-hourly major overhauls

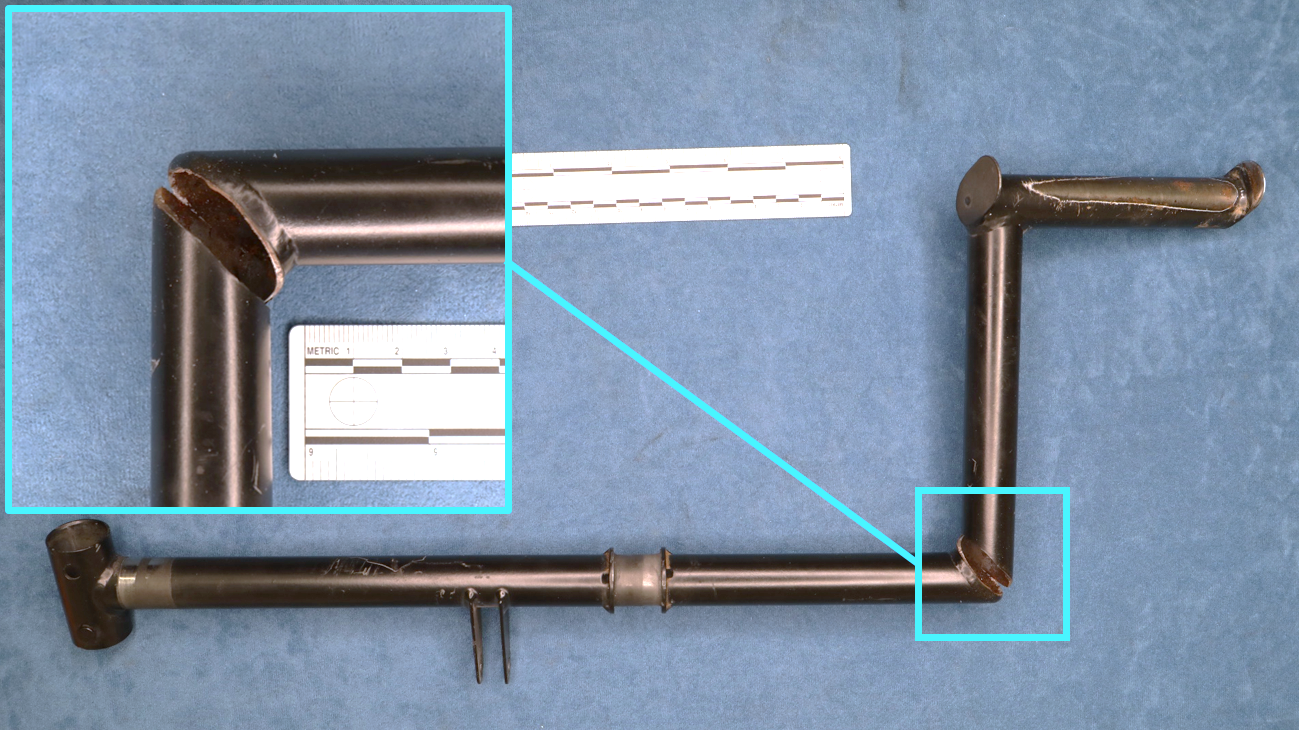
A Robinson R22 helicopter’s right tail rotor pedal failed due to fatigue cracking during mustering operations, an ATSB investigation details.

The R22 was conducting mustering at Kutchera Station in far north Queensland on 22 June 2019, when the pilot applied a small amount of right pedal to turn the helicopter, and the pedal cracked, bent forward and became stuck. The pilot was unable to dislodge the pedal and prepared for an immediate landing in accordance with the stuck pedal procedure. However, just prior to landing, the helicopter struck a tree and became uncontrollable, impacting the ground. While the helicopter was substantially damaged, the pilot was uninjured.

Following the accident, the helicopter’s maintenance organisation identified a significant fracture in the right tail rotor pedal assembly at a right angle weld join between two sections of tube.

The right pedal was then sent to the ATSB’s technical facilities in Canberra. Examination and testing determined that the pedal fracture was a result of a pre-existing fatigue failure, which had initiated at the highest stress part of the welded joint and had opened up following the control input applied by the pilot.

While it was considered likely that the developing crack was present at the time of a recent 100-hourly maintenance inspection, it was not detected, likely due to the location of the weld making it difficult to identify in-situ. The developing crack would have initially presented as a hairline feature, and it was located on a matte black surface, at a change in section slightly below the level of the cabin floor.

“The location of the fatigue crack in this accident highlighted the need to be vigilant when performing inspections in difficult or hard to reach places,” said acting Director Transport Safety Kerri Hughes.

“In the case of the tail rotor pedal, the inspection was made difficult due to the location, and required a torch and mirror to inspect the pedal assembly, which featured a matte black surface.”

While not required as part of the routine inspections, the helicopter’s maintenance organisation has added the tail rotor pedals to the list of components that undergo magnetic particle inspection at each 2,200‑hour overall for the R22.

The investigation also notes the pilot’s positive actions likely contributed to their avoiding any injuries.

“The quick thinking actions of the pilot following the failure resulted in a good outcome, with no injuries sustained,” Ms Hughes said.

Read the final report: Tail rotor pedal failure and collision with terrain involving Robinson R22, VH-HHQ, near Kutchera Station, Queensland, on 22 June 2019

Prop blade collar failure

The fuselage of a Dash 8 turboprop aircraft was penetrated in two places when a propeller blade collar separated shortly after take-off from Darwin.

The DHC-8-202 (Dash 8) aircraft had departed Darwin Airport for aerial work on 3 December 2019 when during the early stages of the climb, the flight crew heard a loud bang. Based on the observations by one crewmember the noise was assumed to be due to a birdstrike. With no issues with controllability and all systems functioning normally, the crew elected to continue the flight, which was undertaken without further incident.

On the ground, a subsequent engineering inspection found that the number 2 blade collar on the right propeller was missing and there was damage to the right propeller and ice shield on the right side of the aircraft fuselage. Removal of the shield revealed the fuselage had been penetrated in two places.

An ATSB investigation identified that the propeller blade collars on the number 2 and number 3 blades had previously undergone field repairs, after having been found loose. Examination of both blades showed evidence of inadequate cleaning and surface reparation on the number 2 blade shank, and that the collar on the number 3 blade was loose due to the presence of adhesive from the field repair.

“It is likely that surface preparation issues from the field repairs resulted in a lack of adhesion between the number 2 blade and its collar, leading to its separation in-flight,” said ATSB Director Transport Safety Stuart Macleod.

“The blade collar then struck the number 1 blade, accelerating the fragments of the collar forcefully into the aircraft's fuselage.”

“This investigation reminds operators and maintenance personnel that due to constraints on equipment, time, and experience, field repairs can be a source of added risk to an aircraft,” said Mr Macleod.

“To minimise risk, maintenance manuals should be closely followed when conducting field repairs and operators should consider alternatives such as replacement over repair whenever practical.”

In response to this incident, the aircraft operator, Cobham Aviation Services Australia, has released an engineering notice requiring the entire blade assembly to be replaced in the event of a loose or cracked blade collar and that if a serviceable blade assembly was not available, collars were to be replaced in consultation with a Technical Services Engineer, and in strict accordance with the component maintenance manual.

Mr Macleod noted that the incident also serves to remind pilots that damage to their aircraft may not always be apparent.

“This occurrence highlights that in‑flight damage may not always be readily apparent to flight crews, and in instances of abnormal noises and vibrations they should seriously consider terminating the flight,” he said.

Read the final report: Propeller blade collar failure involving de Havilland DHC-8, VH-ZZA, near Darwin, Northern Territory, on 3 December 2019

Overhead powerlines dewirement

Key points:

  • Unsecured flat rack end wall extended upwards, dewiring high voltage overhead line equipment
  • During emergency response, risk of close proximity of high voltage overhead line equipment to the flat rack end wall was not identified or controlled.
  • Occurrence highlights the importance of ready access to checklists for rarely completed and emergency response tasks, and effective coordination during an emergency response.

Over a kilometre of overhead powerlines were pulled down when the collapsible end wall of a flat rack container being transported on a freight train extended in transit, contacting an overpass and pulling down the high voltage lines, a new ATSB report details.

The incident occurred on 18 August 2018 when Aurizon-operated intermodal freight train YC77, consisting of a single 2800 class diesel-electric locomotive and 32 flat wagons and crewed by a single driver, was approaching Cooroy, in the Sunshine Coast hinterland, en route from the Acacia Ridge Intermodal Terminal in Brisbane.

Examination of CCTV footage showed that as the train passed through Cooroy, the rear end wall of the top of a stack of three empty flat racks was in the extended position, with overhead line equipment (OHLE), including copper wires, entangled on the wagon and dragging along the station platform. No-one was on the Cooroy station platform at the time of the dewirement, although a southbound passenger train was scheduled to arrive about 30 minutes later.

“The ATSB investigation found that securing of the collapsible end walls of the flat racks was not checked on arrival at the freight terminal or after they were loaded on the train,” said ATSB Director Transport Safety Dr Mike Walker.

“In addition, there was not an effective system in place to ensure personnel required to check the securing of unusual loads, such as empty flat racks, had sufficient knowledge of their responsibilities, or ready access to relevant procedures, guidance and checklists.”

Although the OHLE was de-energised due to the tripping of a circuit breaker during the dewirement, it was not considered electrically safe until it had been isolated, tested and earthed. The ATSB found that on multiple occasions following the dewirement, train crew accessed a three metre exclusion zone associated with the OHLE, prior to the wires being isolated and earthed on site.

Further, network control centre personnel did not advise train crew of the status of the OHLE during the emergency response period, and the infrastructure operator, Queensland Rail (QR), did not have an effective process in place to ensure that safety-critical actions were co-ordinated and completed when multiple network control officers were involved in responding to an OHLE emergency, the investigation notes.

“This occurrence has highlighted the importance of having checklists for rarely conducted tasks and emergency response tasks in the rail environment, and ensuring these checklists are readily available and used by operational personnel,” Dr Walker said.

“This includes checklists for loading and securing personnel, rail traffic crew and network controllers.”

In response to the incident, Aurizon has updated its processes and checklists for the loading of flat racks, provided further training on flat rack securing requirements, and is undertaking a program to improve access to its safety management system, including relevant procedures and checklists. In addition, Aurizon is in the process of drafting procedures related to driver only operations (DOO) on its network.

QR has also mandated the use of a network control officer checklist for OHLE emergencies and is reviewing related aspects of its emergency response procedures. In addition, QR has provided additional training to both network control officers and train crew in relation to identifying objects in close proximity to OHLE and applicable exclusion zones. QR has also taken proactive safety action in the form of further training for NCOs when dealing with emergencies involving a DOO crewing arrangement.

Read the final report: Dewirement involving freight train YC77, Cooroy, Queensland, on 18 August 2018

Wheel rim fracture

Key points:

  • Wheel rim fractured and tyre deflated due to undetected fatigue cracking, a known issue
  • Non-detection likely due to inadequate guidance on inspection requirements for wheels operated with a flat tyre

A Saab 340 main landing gear wheel rim fracture and tyre deflation was likely due to insufficient guidance in the operator’s maintenance procedures for component maintenance inspections, a new ATSB reports says.

On 20 August 2019, a Regional Express Saab 340B, registered VH-ZLX, departed Adelaide, for a scheduled passenger flight to Port Lincoln. During the post flight walk around after landing, the first officer discovered that the left main outboard landing gear tyre was deflated and that a piece of the wheel was missing. The missing section of the wheel was recovered from the runway strip at Adelaide.

The wheel had been fitted to VH-ZLX on the day of the incident, after its removal from another aircraft in July 2019, due to the detection of an audible leak. It was returned to the operator’s maintenance facility with an ‘unserviceable’ tag and ‘repair’ noted on the standard tyre change form. The operation of the wheel with a deflated tyre was not noted.

ATSB examination of the wheel found an area of fatigue cracking had developed in the bead seat region and progressed 86 mm around the circumference before the rim section separated due to overstress, a known issue with this wheel type previously resolved with updated maintenance schedules and practices.  

The large size of the fatigue area along with the relatively low number of flight cycles since its last non-destructive testing indicate the cracking could have been detected following its removal in July 2019.

The ATSB determined that the opportunity to detect the fatigue cracking was limited as the operator’s wheel maintenance forms did not adequately convey the inspection requirements for wheels operated with flat tyres. As a result, inspections that may have detected the crack were not carried out.

The ATSB safety message from this investigation highlights that when situations or issues arise that do not fit into standard operating procedures, maintenance personnel should always be prepared to consult or request further guidance. This guidance can come from internal support materials, such as procedures, or external materials such as maintenance manuals or the manufacturer.

In response to the incident, Regional Express have updated their wheel maintenance procedures to ensure that non-normal inspections are identified and carried out. The airline has also reinforced to maintenance personnel the need to fully complete unserviceable tags to ensure subsequent maintenance personnel fully understand the nature of reported defects.

Read the final report: Landing gear wheel failure involving Saab 340, VH-ZLX, Adelaide Airport, South Australia, on 20 August 2019

Engine surge and vibrations

Key points:

  • Worn bushings led to fretting damage on a lever arm in the fourth-stage variable stator vanes within a General Electric CF6-80E1 engine’s high-pressure compressor
  • Non-mandatory variable stator vane lever arm inspections were not effective in detecting the bushing wear
  • When maintenance organisations carry out additional activities to what is required, they should consider checking with the manufacturer to avoid unintended consequences

An operator’s proactive replacement of worn bushings inadvertently contributed to an Airbus A330’s engine experiencing excessive vibration, an ATSB investigation found.

Shortly after departure from Brisbane Airport on a scheduled flight to Auckland on 15 April 2018, the flight crew of a Qantas Airbus A330-200 received an advisory notification indicating excessive vibration from the left engine. The crew reduced thrust on the left engine to idle, and the noise and vibrations ceased.

The crew elected to return to Brisbane, where the aircraft landed uneventfully. The thrust on the left engine remained at idle during the air turn back.

The ATSB investigation found that worn bushings had led to fretting damage on a lever arm in the fourth-stage variable stator vanes within the General Electric CF6‑80E1 engine’s high-pressure compressor. The lever arm fractured, allowing the variable stator vanes to become off schedule (misaligned), affecting the airflow entering the stage four high-pressure compressor.

The airflow disturbance resulted in abnormal aerodynamic loading and ultimately, fatigue failure of a fourth stage compressor blade. The downstream turbomachinery was then damaged due to the progression of blade debris through the engine.

The ATSB found that three non-mandatory variable stator vane lever arm inspections were carried out prior to the occurrence but were not effective in detecting the bushing wear.

General Electric intended that replacement of the complete set of bushings was required when more than half of the accessible bushings were worn. However, the operator had proactively replaced worn bushings individually when found during maintenance. As a result, the threshold to replace the complete set would not be reached and inaccessible bushings would not be replaced.

As a result of this occurrence, Qantas inspected all CF6-80E1 engines in its A330 fleet for similar defects, with none identified. Additionally, Qantas issued a maintenance memo to service personnel, highlighting the maintenance actions for the variable stator vane system and precautions to be aware of when carrying out work in this area.

The investigation report’s safety message warns that when maintenance organisations carry out additional activities to what is required, they should consider checking with the manufacturer to confirm that no unintended consequences could be introduced.

Read the final report: Engine surge and high vibration involving Airbus A330, VH-EBR, 44 km north-east of Gold Coast Airport, Queensland, on 15 April 2018

Oil sump coking

Key points:

  • Engine failed as a result of an internal oil fire, weakening a turbine disk and resulting in turbine blades being released
  • Fire occurred when oil leaked from an oil sump due to carbon deposits (coking)
  • Maintainers had followed the correct troubleshooting procedure but were unable to determine the reason for the high oil consumption

Coking in an oil sump led to a Saab 340 regional airliner’s right engine failing, a new ATSB investigation has established.

The Regional Express Saab 340B was operating a scheduled passenger service from Moruya to Merimbula on the New South Wales South Coast on 29 August 2019, with the aircraft’s right engine (a GE CT7) being monitored for high oil consumption. About eight minutes into the flight and shortly after levelling off at an altitude of 9,000 feet, the flight crew observed a right engine fire indication. As they conducted the engine fire checklist, the crew heard the engine surge and a loud bang, and the cabin crew member reported seeing a brief flash of light from the aircraft’s right side.

The flight crew continued the engine shutdown checklist and subsequently shut the engine down and elected to continue to Merimbula, based on their proximity to the destination and with the aircraft already having been set up for the approach.

The crew entered a holding pattern to complete all the required checklists and to ensure the availability of emergency services at the Merimbula Airport, where the aircraft landed without further incident.

An ATSB investigation found that the engine failed as a result of an internal oil fire, which weakened a turbine disk and resulted in turbine blades being released. The fire occurred when oil leaked from an oil sump (known as the B-sump) due to carbon deposits, or coking, within that sump. The coking was most likely due to either the sump not being completely clean when installed at the last major overhaul and/or accelerated coking.

As a result of the incident, GE has enhanced the troubleshooting procedures to identify internal engine oil leaks more effectively. They have also developed enhancements to the overhaul facility cleaning procedure for the affected oil sump.

This incident highlights the importance, when piloting multi-engine aircraft, of maintaining the ability to operate with one engine inoperative. Aircraft turbine engines are complex, and can fail for reasons that are rare and difficult to identify prior to the failure, the investigation notes.

In this occurrence, the maintainers had followed the correct troubleshooting procedure but were unable to determine the reason for the high oil consumption. The flight crew’s skill and knowledge, however, along with built-in system redundancies, ensured the overall safety of the flight.

The report notes that there have been only two known occurrences of CT7 engine failures or in-flight shutdowns due to significant coking in the B-sump.

Read the final report: Engine failure involving Saab 340B, VH-RXX, near Merimbula, New South Wales, on 29 August 2019