

Foreign object debris involving Airbus A380, VH-OQK, Sydney Airport, New South Wales, on 9 January 2026
Report release date: 17/08/2026
Investigation summary
What happened
On 7 January 2026, an Airbus A380-842 aircraft, registered VH-OQK and operated by Qantas Airways Limited, arrived at Sydney Airport, New South Wales, from Los Angeles International Airport, United States. Following arrival, maintenance was conducted on the aircraft’s air conditioning system, which required access to an internal area of the left wing.
After the conduct of this maintenance, a work light was inadvertently left in the aircraft wing and the aircraft departed later in the afternoon on a scheduled flight to Dallas Fort Worth International Airport (DFW), United States. The work light was subsequently found following the aircraft’s return to Sydney Airport from DFW on 9 January 2026.
What the ATSB found
The ATSB found that the occurrence resulted from a breakdown in foreign object control and tool accountability processes during and after maintenance. Following maintenance on the air conditioning system, the maintainers did not identify that a work light had remained in the left wing during their foreign object clearance inspections. In addition, while returning the tools, the maintainer did not identify that the work light had not been returned and the unreturned tool check at the end of the shift also did not identify the unreturned light.
The ATSB also found that tool control procedural defences did not prevent the aircraft from being released to service with the unaccounted tool. The licensed aircraft maintenance engineer issued a certificate of release to service (CRS) despite the work light being unaccounted for. Contributing to this, the operator’s maintenance information system did not provide a prompt or control to alert the certifier to the unreturned tool or the unactioned unreturned tool report prior to CRS issue. This allowed the omission to go undetected.
What has been done as a result
Following the occurrence, Qantas released a safety directive to address changes to its tooling control processes and procedures. It has also formed a tooling working group to work on various initiatives, including new technologies, to improve tool control across its various maintenance locations.
Safety message
Foreign object debris and damage poses a significant risk to the safe operation of aircraft. To mitigate this risk, regulations, procedures and training have been developed and refined, particularly to manage the introduction of foreign objects during maintenance. Central to these controls is the effective application of tool control, which serves as a fundamental defence against human error.
However, this occurrence demonstrates that even well-established processes are vulnerable when they rely solely on consistent human performance. Maintenance tasks are often conducted in challenging environments and under operational pressures, and human performance can vary accordingly. Tool control systems and procedures must therefore be designed to account for this variability, incorporating robust checks and safeguards capable of detecting and recovering from errors, particularly during routine or repetitive tasks where the likelihood of oversight may increase.
The occurrence
On 7 January 2026, an Airbus A380-842 (A380) aircraft, registered VH-OQK and operated by Qantas Airways Limited, arrived at Sydney Airport, New South Wales, from Los Angeles International Airport (LAX), United States (US) with 26 crew members and 485 passengers on board. As the aircraft was scheduled to remain on the ground for several hours, maintenance planning had arranged some time for minor defect corrections, including maintenance on the air conditioning system, prior to the aircraft departing on a scheduled flight to Dallas Fort Worth International Airport (DFW), US.
Day 1 – 7 January 2026
The maintenance team at the Sydney International Terminal commenced their shift at 0500 local time, with the A380 crew comprised of one licensed aircraft maintenance engineer (LAME) and 3 aircraft maintenance engineers (AMEs). During the morning, that crew conducted multiple aircraft tows, including unscheduled tows of an Airbus A330 and a Boeing 747‑400. At 0718, VH‑OQK arrived at Bay 10 from LAX, and the maintenance crew commenced engine oil replenishments and post‑arrival inspections. Due to the bay being required for another aircraft, at 0815 the aircraft was towed to the Qantas Jet Base north run-up bay (Figure 1). This tow took approximately 30 minutes to complete.
Figure 1: Sydney Airport key locations
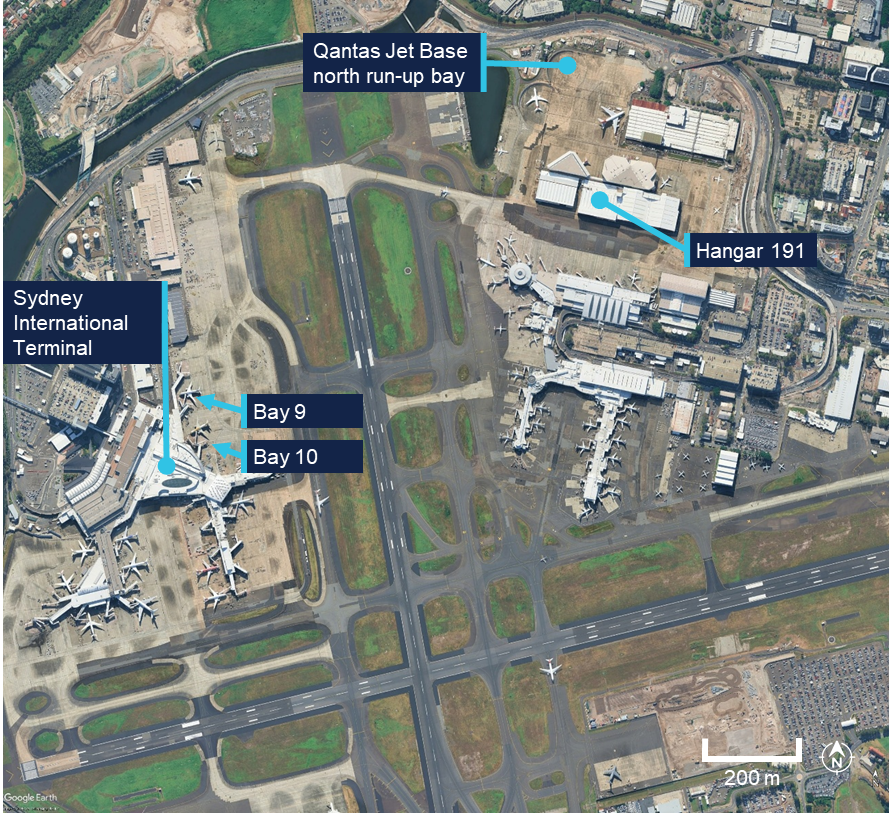
Following the aircraft tow, the LAME and AME 3 commenced work in the cabin to rectify several minor defects. The cleaning crew were also on board at the time, and as the aircraft air conditioning system was inoperative due to required maintenance, there was added pressure on the LAME to restore functionality due to high ambient temperatures (see the section titled Weather).
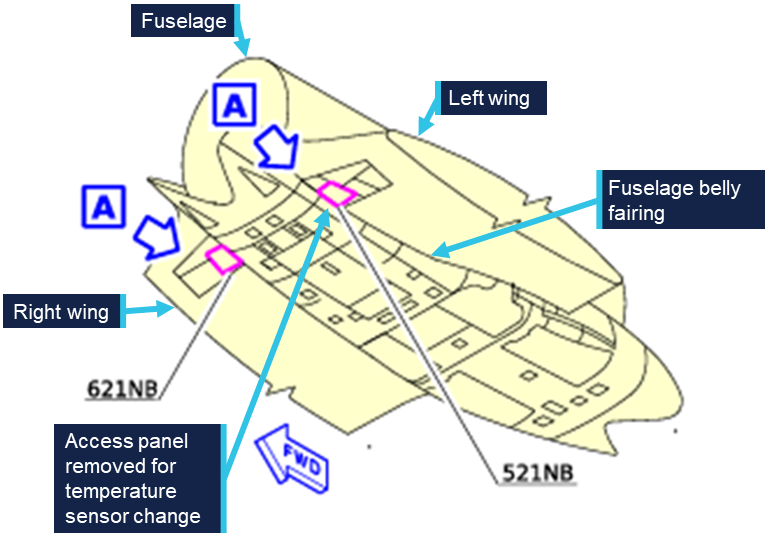
Concurrently, the LAME assigned the 2 AMEs (AME 1 and AME 2) the maintenance task on the air conditioning system. This involved changing an outlet temperature sensor on the air generation unit (AGU) secondary heat exchanger within the left wing. To complete the task, AME 1 signed out tools from the Hangar 191 (Figure 1) tool crib, including a toolbox, screw guns, and a work light. The toolbox and screw guns were signed out against the specific task, and the work light was signed out against the aircraft registration (see the section titled Tool issue and control). At the commencement of the task, an under-wing access panel was removed to allow the maintainers to enter the wing (Figure 4). AME 2 completed the temperature sensor change while AME 1 provided support by passing the required tooling. This included the work light, that was placed inside the wing to illuminate the area.
Following the completion of the temperature sensor change, AME 2 selected the work light power to OFF as they exited the wing. The LAME subsequently conducted an inspection of the work done on the sensor and then proceeded to the flight deck with both AMEs to conduct a test of the air conditioning system. The test required auxiliary power unit (APU) operation, however, the APU unexpectedly failed during start-up. Troubleshooting identified a requirement to bleed the APU fuel system, and AME 1 was sent to obtain an elevated work platform and the required tooling from Hangar 191, resulting in a delay of approximately 30 minutes.
After the APU was successfully started and the testing of the air conditioning system was completed, the LAME returned to the wing and completed a foreign object debris (FOD) clearance inspection with the use of a torch. Subsequently, AME 2 and AME 3 reinstalled the previously removed access panel and AME 1 returned the elevated work platform and tools to the Hangar 191 tool crib.
There was a requirement for the aircraft to be at the departure bay earlier than usual. Consequently, this reduced the time available for maintenance on the aircraft. At approximately 1200, the aircraft was towed back to Bay 9, arriving at around 1245. Shortly after, the LAME departed the aircraft to deal with an unexpected engine maintenance policy change, which required them to return to the office to use the main computer terminal rather than their iPad. While they were away, the AMEs continued departure preparation, including refuelling the aircraft. The LAME subsequently returned to the aircraft while pre-flight preparations were being performed.
At 1321, the LAME completed the maintenance documentation work package and issued a certificate of release to service (CRS) (see the section titled Certification responsibilities). Around 1430, the crew had their first dedicated break since commencing their shift and at 1457, VH‑OQK, operating as QF7, departed for DFW.
Day 2 – 8 January 2026
On 8 January 2026, VH‑OQK arrived in DFW. Maintenance was carried out on the aircraft by a contracted external maintenance organisation and a CRS was issued. This maintenance was carried out under the maintenance organisation’s separate Part 145 approval and did not use the Qantas tool control system. Later that day, the aircraft departed DFW, as QF8, and arrived at Sydney International Airport on 9 January 2026 at 0655.
Day 3 – 9 January 2026
Later that morning after the aircraft had landed, the Hangar 191 tool crib operator reviewed an unreturned tool report, which provided a status of tools currently signed out of the tool crib. They identified that 2 days earlier, a work light had been signed out against VH‑OQK and had not been returned. The tool crib operator notified the duty maintenance manager of the missing tool, who later contacted AME 1, who had signed out the tool. AME 1 could not confirm if the work light had been returned and raised the possibility that it remained in the aircraft wing.
A lost tool search was initiated, and the missing work light was subsequently located inside the wing of the aircraft (Figure 2). No adverse consequences, structural damage, or system disruptions resulted from the work light remaining in the wing.
Figure 2: Work light within wing of aircraft

Context
Conduct of maintenance
Maintenance team and work environment
The A380 maintenance team at the Sydney International Terminal (SIT) usually consisted of 4 maintainers: 1 licensed aircraft maintenance engineer (LAME) and 3 aircraft maintenance engineers (AMEs) involved in the receipt and dispatch of Airbus A380 (A380) aircraft, in addition to other aircraft tasking, depending on staffing levels. The team worked a roster that consisted of 4 days on, 2 day shifts followed by 2 night shifts, and 5 days off. On 7 January 2026, the maintenance team had commenced their first day shift following their rostered off period.
Prior to the start of the shift, the maintenance planning department assigned maintenance tasks to be completed while the aircraft was planned to be on the ground. However, the SIT maintenance work environment was dynamic, consistent with a flightline operation supporting the airline’s schedule, requiring continual adjustments to the planned maintenance tasks. The plan could be further adversely affected when unplanned maintenance issues arose, introducing time pressures and competing priorities. These conditions made it difficult to schedule work tasks and rest breaks at consistent times throughout the shift.
Additionally, staffing levels and the availability of personnel with specific required qualifications could further impact task allocation and workload management. At the commencement of the shift at 0500, only the LAME and AME 1 were assigned to the A380 maintenance team. Both were highly experienced, having worked for the operator as maintainers for 37 years and 22 years respectively. AME 2 and AME 3 were later assigned from the hangar maintenance team. AME 2, who conducted the temperature sensor change, was an experienced maintainer, and had worked for the operator for approximately one year.
Aircraft system
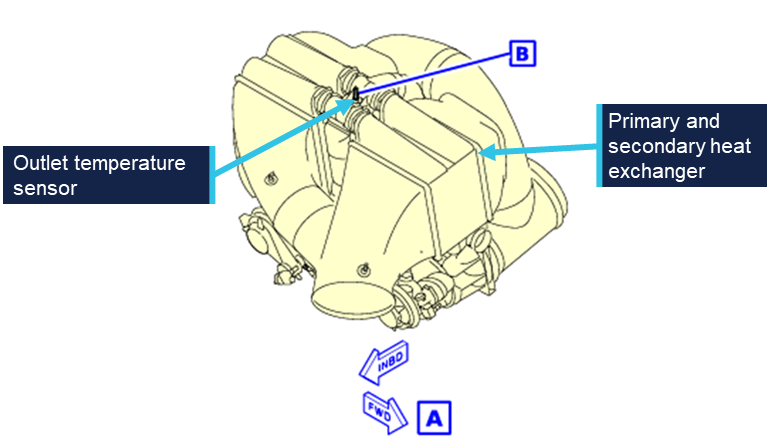
The A380 air conditioning system consists of 2 air generation units (AGUs), also referred to as ‘air conditioning packs’ (Figure 3). Pack 1 is in the inboard left wing and pack 2 in the inboard right wing. The purpose of each AGU is to cool hot engine bleed air before it is distributed for use throughout the aircraft. To achieve this, the AGU incorporates a primary and secondary heat exchanger.
Each heat exchanger is a radiator‑like device that reduces the temperature of the bleed air by passing it through a series of small passages while cooler ambient air flows around them. This process allows heat to be transferred from the hot bleed air to the surrounding airflow, lowering the bleed air temperature without the air streams mixing.
Figure 3: Air generation unit
Maintenance task and conditions
The maintenance task required a change of the outlet temperature sensor on the secondary heat exchanger of the left AGU. The removal of an underwing inboard leading edge access panel (Figure 4) is required to gain access into the wing where the AGU is positioned. A work platform is required to access and remove the panel due to the height of the aircraft’s underside and wing.
The area inside the wing was a confined workspace with limited ambient light, therefore requiring a light source to conduct work (Figure 2). There was space for the maintainers to enter the wing towards the leading edge, however space to work was more restrictive nearer to the AGU. AME 1 reported the workspace inside the wing was warm and stuffy due to the high outside air temperature and residual heat from bleed ducts within the wing. They further recalled that, following the maintenance within the wing, AME 2 was visibly sweating and wanted to get out for a drink of water.
Figure 4: Aircraft access panel location
Weather
Sydney Airport recorded weather data from 7 January 2026 showed the temperature was 27°C at 0900 with scattered cloud cover,1 reducing over the morning. At 1130, the temperature had climbed to 30°C with no cloud cover.
Tooling
The tooling required for the temperature sensor change consisted of a work light, and a combination spanner and a pair of multigrip pliers contained within the signed-out toolbox.
The work light, as shown in Figure 2, was a Makita corded and cordless LED work light capable of being powered by the cord or by attaching a compatible rechargeable battery to allow for portability. During the replacement of the temperature sensor, the work light was powered with an attached battery. The dimensions of the work light were 214 mm (length), 261 mm (width) and 328 mm (height). The work light was predominantly black in colour with a teal backing.
The work light power was found in the off position; however, when turned on, the light functioned normally, indicating that the battery retained sufficient charge.
Tool issue and control
Tool control is a fundamental aspect of aviation maintenance in addition to being a requirement within the Civil Aviation Safety Regulations. Procedures and processes to control tools were required and intended to track tools used on aircraft and the individual using the tools to ensure they were not left on an aircraft.
The process for tool issue and control within the Qantas Engineering maintenance environment commenced when maintenance tasks were assigned within the maintenance information system known as Maintenix (MXI). This system provided maintainers with details related to maintenance tasks, aircraft parts and the tooling required to complete the task. Each task was identified by a unique barcode.
Tooling was centrally stored in a tool crib and a tool crib operator provided oversight over the issuing and returning of the tools.2 The tooling was required to be signed out to the individual maintainer and linked to the specific aircraft or aircraft task by scanning the barcode on the specific tools against the task barcode or the barcode for the aircraft registration and the individual. This ensured the signed‑out tooling was recorded in the maintenance information system. The status of signed-out tooling was viewable using an unreturned tool report that identified any tooling signed out to a task, a maintainer or an aircraft registration. However, the report gave a status at a given time it was generated and did not retain a permanent record.
Upon completion of the maintenance task, the maintainer conducting the task was responsible for ensuring all tooling was removed from the aircraft. In addition, a mandatory clearance inspection was required to be conducted by the certifier to confirm that the work area, and therefore aircraft, was free from tools or foreign objects.
Only once the clearance inspection was completed, and tooling accounted for, could the maintenance task proceed to certification. The use of the unreturned tool report was the preferred means to account for tools prior to certifying for the maintenance and issuing a certificate of release to service (CRS). While this procedure was well known to the LAME, they had later realised that on this occasion they had not generated and reviewed the unreturned tool report for the aircraft prior to issuing the CRS.
If there were tools identified on the unreturned tool report at this stage, the procedure stated:
If there is any tooling listed on the AMO [approved maintenance organisation] UTR [unreturned tool report] then the whereabouts of this tooling needs to be confirmed as not posing a risk.
In addition, the operator’s company and personal tool policy stated:
The Duty Maintenance Managers, Shift Managers, Maintenance Supervisors / Crew Leaders or Maintenance Airworthiness & Safety Controllers (MASC) shall ensure maintenance employees under their control carry out a full tooling inventory check at the end of shift.
Any tools identified as unaccounted for became ‘lost tools’ and a search procedure was to be followed to locate and retrieve the tools.
There was no requirement for the tool crib operators to use the unreturned tool report during, or at the end of, the shift, to account for tools that had not been returned. The tool crib employee advised that the unreturned tool report was used to gain situation awareness of signed out tools, run either at the start of a shift or every 48 hours.
Certification responsibilities
Under the Civil Aviation Safety Regulations (CASRs) Part 42.330, the individual who carries out the maintenance task was required to remove any tools or equipment before a CRS was issued for the aircraft. The Civil Aviation Safety Authority (CASA) provided acceptable means of compliance (AMC) to regulation 42.330, which included the use of a shadow board,3 electronic tool and equipment management system, or tool and equipment audit system to ensure all tooling has been removed from the aircraft.
To meet the CASRs for the conduct and certification of maintenance, the operator’s procedure for the Certificate of release to service detailed that:
A CRS must be issued following any maintenance activity and related maintenance certification. This includes any certified entry in the logbooks or the MIS.
Part of the maintainer’s responsibilities when issuing a CRS included:
Verify that all tools and equipment have been removed from the aircraft and accounted for (CASR 42.330). AMO Unreturned Tool Report are available from the MIS and should be used.
Related occurrence
AO-2024-006
On 6 December 2023, an Airbus A380-842 aircraft, registered VH‑OQI and operated by Qantas Airways Limited, was undergoing a 3-day scheduled maintenance check at Los Angeles International Airport (LAX), United States. On day one of the maintenance check, during a scheduled borescope inspection of the outboard left engine, a tool was left in the engine inlet.
On 1 January 2024, the aircraft returned to the LAX maintenance facility for a 3-day scheduled maintenance check, where the missing tool was discovered in the outboard left engine low‑pressure compressor. The aircraft had flown 34 cycles totalling 293.74 hours with the tool in the outboard left engine.
Safety analysis
Foreign object clearance inspections and tool return
At the conclusion of the maintenance task to change the outlet temperature sensor on the air generation unit inside the left wing of the Airbus A380, aircraft maintenance engineer (AME) 1, AME 2 and the licensed aircraft maintenance engineer (LAME) did not observe the work light that remained in the left wing during their foreign object clearance inspections. It’s likely that the work light was not identified in part due to:
- The work light had been selected off when the crew went to the cockpit to run the air conditioning unit.
- The confined workspace within the wing with low lighting combined with the work light colours making it difficult to visually identify.
- The high temperature within the confined workspace likely reducing the time spent conducting the clearance inspections.
Contributing factor The aircraft maintenance engineers and licensed aircraft maintenance engineer did not observe a work light that remained in the left wing during their foreign object clearance inspections following maintenance on the aircraft air conditioning system. |
Given the unplanned interruption and additional maintenance activity related to the auxiliary power unit (APU), it is likely that when AME 1 later returned the tools to the tool crib, they had reduced ability to recall all items used during the outlet temperature sensor replacement. Additionally, this ability to recall the tools used in the task was likely also influenced by the work light not being a tool physically used in the task, but rather a passive tool used to illuminate the workspace.
Contributing factor In part due to the type of tool used during the temperature sensor change, and the follow-on troubleshooting needed on the auxiliary power unit, the aircraft maintenance engineer returned the tools to the tool crib without realising that the work light was still signed out and not returned. |
At the conclusion of the shift, neither AME 1 or their supervisor identified that the work light had not been returned and remained signed out to AME 1. The ATSB was unable to identify if the unreturned tool report was reviewed at the conclusion of the shift or the light was missed during the review. While the CRS had already been issued and the aircraft had departed for Dallas Fort Worth International Airport (DFW) prior to the end of the shift, the end of shift tool return check represented another opportunity where the work light could have been identified as missing and removed while on the ground at DFW.
Other factor that increased risk At the end of the shift, it was not identified that a tool had not been returned and remained signed out to the aircraft maintenance engineer. |
Unreturned tool report check
At the completion of maintenance, following the clearance inspections and prior to issuing the certificate of release to service (CRS), the unreturned tool report was the preferred means for the certifier to account for all tooling used during maintenance. While this process was well known and routinely performed by the LAME, they later realised that on this occasion they had not generated and reviewed the unreturned tool report for the aircraft prior to issuing the CRS.
This omission, within a routinely performed task, was likely influenced in part by attention being diverted during the departure preparations for the aircraft, whereby the LAME had an unexpected maintenance task, and they were supervising the AMEs while concurrent pre-flight activities were being conducted. Consequently, the CRS was issued with the work light unaccounted for and the aircraft flew 2 sectors with the work light in the left wing.
Contributing factor The licensed aircraft maintenance engineer issued a certificate of release to service with a tool unaccounted for. As a result, the aircraft flew 2 sectors with the work light in the left wing. |
The action of checking the unreturned tool report, prior to issuing a CRS, was documented within the engineering procedures and was well known to the LAME. This procedure did, however, create the requirement for engineers to manually initiate and review the unreturned tool report within the maintenance information system (MXI). This made the process vulnerable to omissions whereby a CRS could be issued without review of the unreturned tool report. Furthermore, the design of the MXI system meant that there was no way to prompt or identify to the certifier that either tools were still signed out to the aircraft or that the unreturned tool report had not been reviewed.
Contributing factor Qantas Engineering’s maintenance information system did not have an automated way to identify to the certifier, prior to issuing the certificate of release to service, that tools used on the aircraft were unreturned or that the unreturned tool report had not been actioned. (Safety issue) |
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time. These findings should not be read as apportioning blame or liability to any particular organisation or individual. |
From the evidence available, the following findings are made with respect to the foreign object debris involving Airbus A380, VH-OQK, at Sydney Airport, New South Wales, on 9 January 2026.
Contributing factors
- The aircraft maintenance engineers and licensed aircraft maintenance engineer did not observe a work light that remained in the left wing during their foreign object clearance inspections following maintenance on the aircraft air conditioning system.
- In part due to the type of tool used during the temperature sensor change, and the follow-on troubleshooting needed on the auxiliary power unit, the aircraft maintenance engineer returned the tools to the tool crib without realising that the work light was still signed out and not returned.
- The licensed aircraft maintenance engineer issued a certificate of release to service with a tool unaccounted for. As a result, the aircraft flew 2 sectors with the work light in the left wing.
- Qantas Engineering’s maintenance information system did not have an automated way to identify to the certifier, prior to issuing the certificate of release to service, that tools used on the aircraft were unreturned or that the unreturned tool report had not been actioned. (Safety issue)
Other factors that increased risk
- At the end of the shift, it was not identified that a tool had not been returned and remained signed out to the aircraft maintenance engineer.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies. Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation. Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action. |
Unreturned tool report
Safety issue number: AO-2026-004-SI-01
Safety issue description: The operator's maintenance information system did not have an automated way to identify to the certifier, prior to issuing the certificate of release to service, that tools used on the aircraft were unreturned or that the unreturned tool report had not been actioned.
Glossary
| AGU | Air generation unit |
| AMC | Acceptable means of compliance |
| AME | Aircraft maintenance engineer |
| APU | Auxiliary power unit |
| CASA | Civil Aviation Safety Authority |
| CASR | Civil Aviation Safety Regulations |
| CRS | Certificate of Release to Service |
| DFW | Dallas Fort Worth International Airport |
| FOD | Foreign object debris |
| LAME | Licenced aircraft maintenance engineer |
| LAX | Los Angeles International Airport |
| LED | Light-emitting diode |
| MXI | Maintenix |
| SIT | Sydney International Terminal |
| US | United States |
Sources and submissions
Sources of information
The sources of information during the investigation included:
- Qantas Airways Limited
- the aircraft maintenance engineers directly involved in the task
- the tool crib operator who identified the missing tool.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
- Qantas Airways Limited
- the aircraft maintenance engineers directly involved in the task
- the tool crib employee who identified the missing tool
- Civil Aviation Safety Authority.
Submissions were received from:
- an aircraft maintenance engineer directly involved in the task
- Qantas Airways Limited.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigationsThe objective of an ATSB safety investigation is to improve transport safety through:
In accordance with the TSI Act, the ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action, and cannot apportion blame, assist in determining liability, or, as a general rule, assist in court proceedings. About ATSB reportsATSB safety investigation reports are developed in accordance with ATSB procedures and guidelines, and with regard to applicable international standards and instruments. Reports must include factual material of sufficient weight to support the investigation’s analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. An explanation of terminology used in ATSB investigation reports is available here. Publishing informationReleased in accordance with section 25 of the Transport Safety Investigation Act 2003 Published by: Australian Transport Safety Bureau © Commonwealth of Australia 2026 Ownership of intellectual property rights in this publication Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia. Creative Commons licence 
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence. The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly. |
- ^ Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘scattered’ indicates that cloud is covering between a quarter and a half of the sky.
- ^ There were also allowances in the procedures for tooling to be issued without a tool crib employee present.
- ^ A shadow board is a visual tool control system where each tool has a clearly marked position, allowing users to quickly identify missing items and ensuring all tools are returned and accounted for.
Occurrence summary
| Investigation number | AO-2026-004 |
|---|---|
| Occurrence date | 09/01/2026 |
| Occurrence time and timezone | 15:00 Australian Eastern Daylight Time |
| Location | Sydney Airport |
| State | New South Wales |
| Report release date | 17/08/2026 |
| Report status | Final |
| Investigation level | Defined |
| Investigation type | Occurrence Investigation |
| Investigation phase | Final report: Dissemination |
| Investigation status | Completed |
| Mode of transport | Aviation |
| Aviation occurrence category | Foreign object damage / debris |
| Occurrence class | Incident |
| Highest injury level | None |
Aircraft details
| Manufacturer | Airbus |
|---|---|
| Model | A380-842 |
| Registration | VH-OQK |
| Serial number | 63 |
| Aircraft operator | Qantas Airways Limited |
| Sector | Jet |
| Operation type | Part 121 Air transport operations - larger aeroplanes |
| Activity | Commercial air transport-Scheduled-International |
| Departure point | Dallas/Fort Worth International Airport, United States of America |
| Destination | Sydney Airport, New South Wales |
| Injuries | None |
| Damage | Nil |
Hard landing and runway excursion involving a Cessna 150H, West Sale Airport, Victoria, on 22 December 2025
What happened
On 22 December 2025 at 1640, a pilot was conducting circuit operations with one passenger on board a Cessna 150H at West Sale Airport, Victoria.
In contrast to the recorded weather conditions, the pilot identified a left-hand crosswind via the aerodrome windsock for the one runway available. Alternate grass runways were unavailable due to rain in the preceding 24 hours.
During landing in the crosswind on runway 27, the pilot ‘crabbed’ by yawing[1] the nose of the aircraft into the wind to prevent the aircraft from drifting off the centreline. The pilot assessed that the approach was stable and proceeded to touch down. During rollout, after the flare, the aircraft encountered a gusting wind, resulting in the aircraft ballooning[2] and yawing to the right. In response, the pilot attempted to counteract with a left yaw. However, the conditions exceeded the aircraft’s capabilities and the aircraft was carried to the right, and the right wheel contacted the runway surface. The right main landing gear collapsed, and the right wing tip struck the ground before the aircraft veered off the runway.
The pilot and passenger exited the aircraft without injuries, and the aircraft was substantially damaged (Figure 1).
Figure 1: Damage to the Cessna 150H right landing gear

Source: Aircraft owner
Safety message
Crosswind gusts during the later stages of landing can present challenges for pilots. Depending on the magnitude and direction of the gust, there may be insufficient time to apply corrective controls before the aircraft deviates from the intended path.
Once the aircraft wheels touch down, it's important to remain focused and use your rudder to keep the aircraft straight, even after you have touched down, to retain control and stability.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence summary
| Mode of transport | Aviation |
|---|---|
| Occurrence ID | AB-2026-001 |
| Occurrence date | 22/12/2025 |
| Location | West Sale Airport |
| State | Victoria |
| Occurrence class | Accident |
| Aviation occurrence category | Control issues, Hard landing, Runway excursion |
| Highest injury level | None |
| Brief release date | 23/01/2026 |
Aircraft details
| Manufacturer | Cessna Aircraft Company |
|---|---|
| Model | 150H |
| Sector | Piston |
| Operation type | Part 91 General operating and flight rules |
| Damage | Substantial |
Forced landing after engine failure in Piper Cherokee
A Piper Cherokee conducted a forced landing on a Sydney golf course after an exhaust valve broke in the aircraft’s engine, resulting in a rapid loss of power, an ATSB investigation has found.
The accident occurred during a 17 August 2025 navigation training flight, which had taken off from Wollongong (Shellharbour) Airport with a student pilot and an instructor on board.
While around 1,600 ft above the coast north of Sydney, the crew heard unusual noises and observed a rapid drop in engine RPM.
“Fortunately, the instructor was proactive in maintaining an awareness of potential landing sites throughout the flight,” ATSB Chief Commissioner Angus Mitchell said.
The report notes the instructor initially wanted to reach Long Reef golf course, with fewer trees, but maintained awareness of Mona Vale golf course being closer in case engine performance worsened.
“About six minutes into the occurrence, as the engine RPM progressively decreased, the instructor was able to determine that the safest option would be to conduct a landing on the Mona Vale golf course,” Mr Mitchell said.
During the final stages of the approach, however, the pilot realised they had positioned the aircraft such that they could not safely land straight ahead, and so made a right turn to avoid the golf course facilities.
During the turn the right wing dropped. The aircraft subsequently landed heavily, resulting in substantial damage, and minor injuries to the student pilot.
Nonetheless, Mr Mitchell said, the pilot’s prompt identification of a suitable forced landing site meant a worse potential outcome was avoided.
“This investigation highlights the importance of effective decision-making skills in emergency situations,” he said.
The source of the engine failure was found to be the exhaust valve of the engine’s number 3 cylinder, which broke away from its stem and caused extensive damage to the internal surfaces of the cylinder, its piston and spark plugs.
In this case, the cause of the exhaust valve failure could not be determined. However, the ATSB’s final report notes the engine’s manufacturer, Textron Lycoming, has provided maintenance practices to reduce the possibility of valve sticking.
“Operators and maintainers should be aware the risk of valve sticking is increased for engines operating in hot ambient conditions, and where engines are regularly shut down before they have cooled sufficiently,” Mr Mitchell concluded.
After the accident, the training operator undertook several safety actions, including revising its emergency briefing content, completing a review of competency in conducting engine failure procedures for its instructors, and commencing a process to check students’ post-engine failure competencies.
Read the final report: Loss of power and forced landing involving Piper PA-28, VH-BUN, 32 km north-north-east of Sydney Airport, New South Wales, on 17 August 2025
Cressy level crossing collision
A transport safety investigation has been launched into a collision between a utility vehicle and a freight train at a level crossing in western Victoria on Tuesday morning.
The collision occurred around 10:15 am local time at the Reddies Road passive level crossing at Cressy. Tragically, two people in the utility vehicle were fatally injured. The train drivers were not physically injured, and the train remained on the tracks.
The independent, ‘no blame’ transport safety investigation will be conducted by Victoria’s Office of the Chief Investigator under a collaboration agreement with the Australian Transport Safety Bureau.
A team of investigators arrived on site on Tuesday afternoon to commence the investigation.
A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the investigation, relevant parties will be notified immediately, so that appropriate safety action can be taken.
Background: The Office of the Chief Investigator (OCI) is the operational office of the Chief Investigator, Transport Safety, a statutory position established in the Transport Integration Act 2010 (Vic) to provide independent, no blame investigation of transport safety matters in Victoria.
OCI can investigate rail occurrences in Victoria under the Transport Safety Investigation Act 2003 (Cth), under a collaboration agreement with the Australian Transport Safety Bureau.
The ATSB is Australia’s national transport safety investigator, and conducts no blame aviation, rail and marine transport safety investigations to help prevent the occurrence of similar future accidents.
Runway excursion and collision with terrain involving an Air Tractor AT-802A, 82 km north-west of Hopetoun, Victoria, on 4 December 2025
What happened
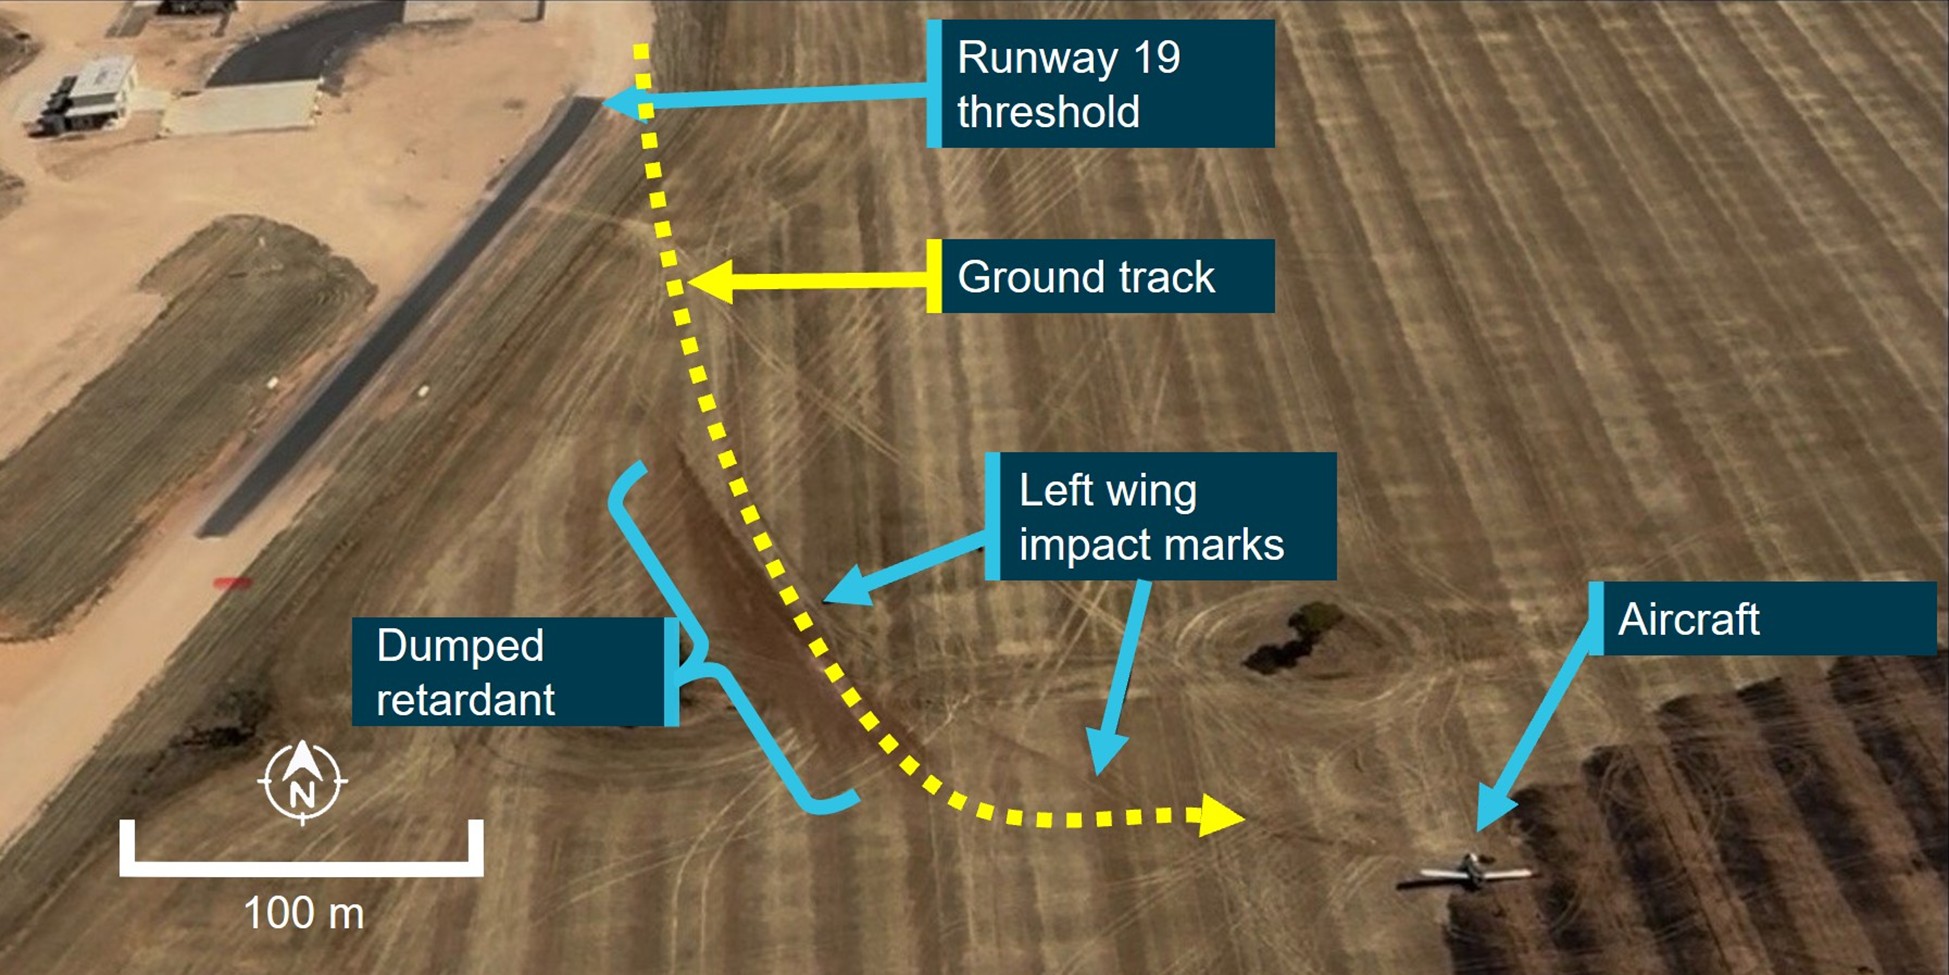
On 4 December 2025, at 1720 local time, an Air Tractor AT-802A was preparing to conduct aerial firefighting operations from Linga Airbase, Victoria. Before departure the pilot briefly consulted electronic maps for Linga Airbase, however, did not observe that runways 17 and 19 were 2 separate runways with runway 19 commencing at the end of runway 17 rather than a single longer runway (Figure 1). After loading the aircraft with fire retardant, the pilot commenced taxi for runway 17, believing they were backtracking to use the entire length of runways 17 and 19. The pilot completed their take-off checks and commenced the take-off roll.
The pilot reported that during the take-off run, due to the upslope on runway 17, they were unable to see the threshold of runway 19 until the aircraft had crested the rise towards the end of runway 17. Unaware of the 20° right turn, on becoming visual with runway 19, the pilot assessed the turn was too sharp to navigate and the aircraft was travelling too fast to stop and not yet fast enough to become airborne.
Figure 1: Linga Airbase, Victoria
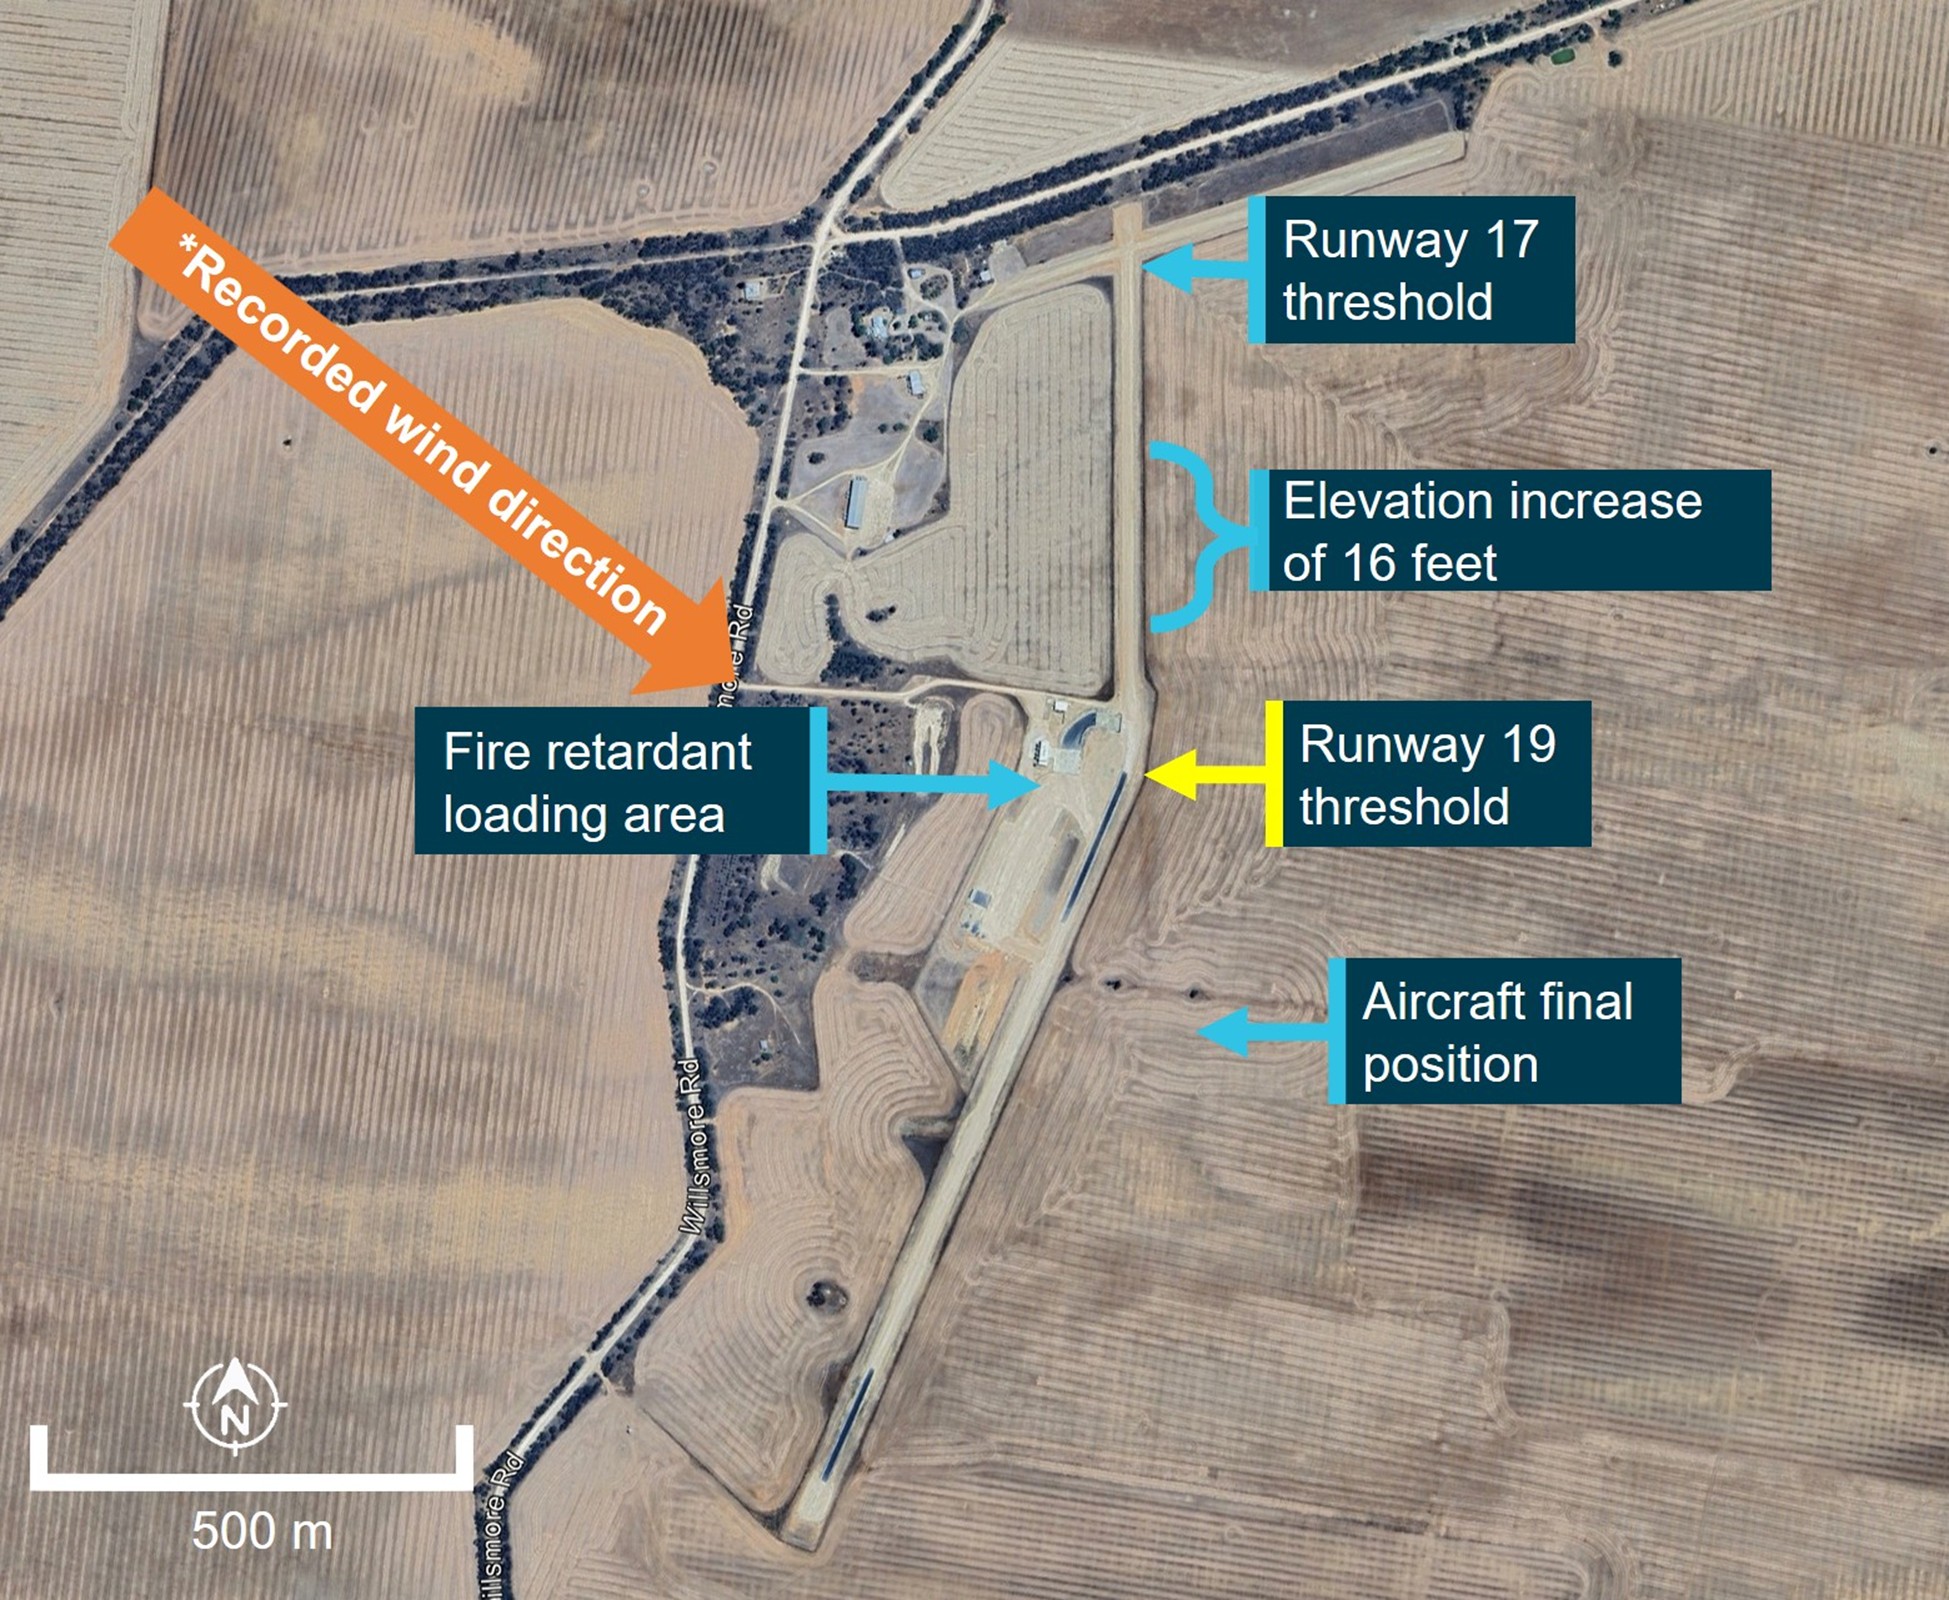
* Wind direction was recorded 82 km away at Hopetoun, Victoria. Source: Google Earth, annotated by the ATSB
The pilot maintained the runway 17 heading, and the aircraft overran the end of runway 17 into a field, impacting a fence, before becoming airborne. The pilot intended to release the load of fire retardant to reduce weight, however, due to their unfamiliarity with the location of the load release switch in that aircraft, instead activated the aircraft lights, before locating the correct switch and dumping the load. Images show the left-wing tip dragged along the surface of the field while the load was dumped. A witness reported the aircraft briefly became airborne with a nose high attitude and left wing down in a left turn before the left wing again contacted the ground and pulled the aircraft to the ground before coming to a stop (Figure 2).
Figure 2: Occurrence aircraft impact marks and final position
Source: Operator, annotated by the ATSB
The impact was sufficient to liberate the engine and propeller from the aircraft which subsequently set fire to the field (Figure 3). The local airbase manager and 2 other state government employees attended the scene and were able to put the fire out in the vicinity of the aircraft and were then able to assist the pilot to egress the aircraft.
The pilot sustained minor injuries and was admitted to Mildura hospital. The aircraft was substantially damaged.

Source: Operator
The pilot reported that they had not previously operated from Linga Airbase, and earlier when arriving in the circuit they joined a midfield crosswind leg for runway 01 before landing, and had not observed the angle of the adjoining runways from the air.
The airbase manager reported other firefighting aircraft had been using runway 19 throughout the day. Linga Airbase runway 17 was about 660 m in length and joined the northern end of runway 19 which measured about 1,000 m in length. The aircraft was loaded with retardant to the western side of where runways 17 and 19 met.
The pilot reported the wind direction during the take-off roll was a crosswind. Conditions around the time of the occurrence recorded at Hopetoun, Victoria indicated temperature of 38°C with winds gusting between 16–33 kt from the north-west.
The aircraft loading log for the day of the occurrence indicated it was loaded with about 2,300 L of fire retardant. This gave the aircraft a take-off weight of about 6,900 kg, which was below the aircraft’s maximum take-off weight for the conditions. The operator reported the aircraft’s performance in the hot conditions required a take-off ground roll distance of about 1,000 m.
Although they were an experienced agricultural pilot, they had not previously operated from that airbase. Although the pilot observed other aircraft depart using runway 19 while reloading, they assumed they were not using the entire length of the runway, and by taxiing and backtracking to the threshold of runway 17 believed they were increasing their take-off roll distance. Performance calculations indicated that due to the air temperature, weight of the aircraft and wind conditions, the aircraft would have required the full length of the longer runway 19 to become airborne.
Safety message

The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. One of the safety concerns is reducing the severity of injuries in accidents involving small aircraft. As a result of the aircraft’s sudden stop the pilot’s flight helmet was damaged in the occurrence and they suffered a laceration to their head. Therefore, it was likely the pilot’s helmet prevented a more serious head injury.
Thorough pre-flight planning is essential to safe flight and is especially important when operating from unfamiliar airports. A clear understanding of the take-off distances available and runway configuration improves pilots’ situational awareness, reducing the possibility of the unexpected during higher risk stages of flight such as take-off and landing.
Aerial firefighting operations are often conducted in conditions of extreme heat and wind; accurate performance calculations including take-off weight and available runway distance are essential for safe operations in challenging conditions.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence summary
| Mode of transport | Aviation |
|---|---|
| Occurrence ID | AB-2025-065 |
| Occurrence date | 04/12/2025 |
| Location | 82 km north-west of Hopetoun |
| State | Victoria |
| Occurrence class | Accident |
| Aviation occurrence category | Collision with terrain, Runway excursion |
| Highest injury level | Minor |
| Brief release date | 21/01/2026 |
Aircraft details
| Manufacturer | Air Tractor Inc |
|---|---|
| Model | AT-208 |
| Sector | Turboprop |
| Operation type | Part 138 Aerial work operations |
| Damage | Substantial |
Non-specific pre-flight inspection procedures contributed to pitot covers incident

Poor visibility, an incorrect assumption, and non-specific operator procedures contributed to a Metroliner freight aircraft taking off from Townsville with both of its pitot tubes still covered, an ATSB final report details.
The incident occurred at night, in heavy rain on 10 February 2025, when the Fairchild SA227 twin turboprop was being prepared for a freight flight from Townsville to Brisbane, Queensland.
The same aircraft had been flown into Townsville by the same captain and first officer on the morning of the incident. After landing in Townsville around 0800, the flight crew had conducted a terminating check and installed engine bungs, static port covers, and pitot tube covers, before ending their duty and spending the day resting.
After coming back onto duty shortly after 1800, the flight crew began to prepare the aircraft for its return trip to Brisbane.
The first officer removed the engine bungs and static port covers, but was unable to reach the pitot tube covers, so asked the captain to remove them. The captain said they would remove the tube covers but subsequently forgot.
The first officer incorrectly assumed the captain had removed the covers, and the flight crew proceeded to taxi for take-off.
Due to the conditions, neither crew could see the pitot tube covers on the nose of the aircraft during their taxi.
“The flight crew recognised slowly rising airspeed indications during the take-off roll but did not identify that this was symptomatic of blocked pitot tubes,” ATSB Director of Transport Safety Stuart Macleod said.
Observing the aircraft’s groundspeed on a separate GPS unit, and uncertain if there was sufficient runway in wet weather to safely stop, the captain elected to continue the take-off.
During the climb, the flight crew became aware the pitot covers had been left installed on the pitot tubes. The crew was then able to return to Townsville for an uneventful landing.
“This occurrence highlights the importance of conducting an airspeed check early in the take-off run and recognising if something is not as expected, so the take-off can be safely rejected,” Mr Macleod said.
He said the occurrence also highlighted a discrepancy between the operator’s expectations and what was detailed in its procedures.
“When the flight crew began their evening shift shortly after 1800, the captain did not believe a daily inspection was required, as one had already been completed earlier that day,” Mr Macleod explained.
“They also believed a crew change inspection was not required, as the crew had not changed.”
The aircraft operator, Sharp Airlines, stated it expected a full daily inspection of the aircraft was required after termination checks had been completed, but this was not stated in its procedures.
Further, the final visual check conducted by the first officer prior to closing the doors, as stated in the procedures, did not include checking the pitot covers had been removed.
Sharp Airlines has advised it is reviewing the standard operating procedures to ensure clarity of process for pre-flight inspections.
“This scenario illustrates the importance of procedures clearly stating what inspections are required, and when,” Mr Macleod said.
“Flight crew pre-flight inspections are an important risk control, but if they are not done correctly, it increases the risk of defects not being identified, and/or the aircraft not being correctly configured for flight.”
Read the report: Unreliable airspeed indication on take-off involving Fairchild SA227, VH-UZN, Townsville Airport, Queensland, on 10 February 2025