Spatial disorientation

Key points:

  • Flight operated under visual flight rules and required a transit over the McPherson Range
  • Aircraft encountered reduced visibility and the pilot likely became spatially disorientated, resulting in a loss of control
  • Weather-related decision making can be highly complex

The pilot of a Wittman Tailwind light aircraft that impacted a ridgeline in the Tooloom National Park near the NSW-Queensland border on 12 January 2020 likely became spatially disorientated after encountering poor weather, an ATSB investigation has found.

The aircraft, with the owner-pilot and a passenger on-board, was returning from a fly-in at Evans Head in northern New South Wales that had been curtailed due to poor forecast weather conditions. Their flight to Boonah in Queensland required a transit over the McPherson Range, which varies in altitude with several areas above 3,000 feet above sea level and some peaks above 4,000 feet.

The ATSB investigation into the accident established that the aircraft departed Evans Head shortly after 130 pm and tracked north towards Boonah via the Richmond River valley. About 17 minutes into the flight the pilot commenced a 180° turn overhead the township of Kyogle and diverted south back down the valley to Casino, landing there shortly after 2 pm.

That initial flight from Evans Head indicated that the pilot was attempting to cross the ranges via a route known as the ‘border loop’, which is commonly used by VFR (visual flight rules) pilots to transit the range.

On the ground in Casino, the pilot left a voicemail message for a friend in which they stated they could not get past Kyogle due to the weather, so they had landed at Casino.

Shortly before 3 pm, the aircraft took off from Casino and flew in a west-north-westerly direction, which indicated the pilot was attempting to cross the range via another common VFR route, which involved tracking via the Toonumbar Dam, then Killarney to Warwick.

At 310 pm, recorded data showed that the aircraft commenced a series of rapid descents and climbs, between 3,100 and 4,000 feet, followed by a left descending turn, before shortly afterwards impacting terrain in dense rainforest. The pilot and passenger were fatally injured and the aircraft was destroyed.

“The ATSB found that the pilot, who was operating under visual flight rules, departed Casino with a high risk of encountering forecast cloud,” said ATSB Director Transport Safety Stuart Macleod.

Data from the last four minutes of the flight showed the aircraft’s groundspeed speed varied between 109 and 175 knots, while the aircraft’s rate of climb and descent varied between +2,400 feet/min and -2,400 feet/min.

“En route to Boonah, the aircraft encountered reduced visibility and the pilot likely became spatially disorientated, resulting in a loss of control.”

The abrupt speed and altitude reversals and the operation of the aircraft over and near its speed limitations were indicative of a loss of control, the investigation notes.

A final data point showed the aircraft descending at 1,800 feet/min while travelling at a groundspeed of 172 knots and tracking towards high ground.

Spatial disorientation occurs when the brain receives conflicting or ambiguous information from the sensory systems, Mr Macleod noted. It is likely to happen in conditions in which visual cues are poor or absent, such as in adverse weather or at night.

“Once airborne, the pilot would have been in a position to assess the in-flight visibility and cloud and rain in the intended direction of travel. However, it is possible that continuing to fly towards an area of low cloud was influenced by the inherent challenges of assessing low visibility conditions,” said Mr Macleod.

“Weather-related decision making can be highly complex and therefore more prone to errors,” he stressed.

“Unfortunately, weather-related general aviation accidents remain one of the ATSB’s most significant causes for concern.”

A recent ATSB safety education campaing titled Don’t push it, DON'T GO - know your limits before flight was developed to remind VFR pilots of the dangers of flying into IMC and to highlight the actions they can take to avoid a weather-related accident, Mr Macleod noted.

That campaign highlights three key messages: the importance of thorough pre-flight planning and having alternate plans, that pressing on and entering instrument metereological conditions (IMC) carries a significant risk of spatial disorientation, and the value of using a ‘personal minimums’ checklist to help manage flight risks.

“Pilots without a current instrument rating should always be prepared to amend and delay plans to fly due to poor or deteriorating weather conditions, and not to push on,” Mr Macleod stressed.

“In this case the pilot initially did make a sound decision to divert to Casino and turn back from the first attempt to cross the ranges, demonstrating an awareness of the risk posed by the weather and the need to maintain visual reference.”

The pilot’s subsequent decision to depart Casino can be interpreted as likely taking advantage of acceptable conditions there with the notion that the weather further inland may have allowed for VFR flight over the ranges, the investigation notes.

“The ATSB encourages VFR pilots to build a robust understanding of the risks of flying into IMC and just how rapidly spatial disorientation accidents can happen,” said Mr Macleod.

Findings from other ATSB investigations into accidents where VFR pilots entered IMC were published in the ATSB’s recently updated Accidents involving Visual Flight Rules pilots in Instrument Meteorological Conditions publication.

Read the final report: VFR into IMC and loss of control involving Wittman Tailwind, VH‑TWQ, Tooloom National Park, New South Wales on 12 January 2020.

Effective management of risks

Key points:

  • Helicopter experienced an immediate power loss while operating at low-level due to an air line leak created by a loose union
  • A range of factors exacerbating the occupants’ injuries
  • Contracting agency did not actively manage or effectively supervise the culling operation

The Australian Transport Safety Bureau’s (ATSB) investigation into the collision with terrain of a Bell JetRanger helicopter during feral animal culling highlights the importance of independent inspections following maintenance and the effective management of risks for low-level aerial shooting operations.

The accident occurred in the Kakadu National Park, Northern Territory on the morning of 21 May 2019 when JetRanger VH-FHW, with a pilot, shooter and spotter on board, was tasked to cull a mob of feral horses. The helicopter was operated by Jayrow Helicopters under contract to the Director of National Parks (DNP), while the shooter and spotter were experienced Kakadu National Park rangers.

The helicopter was at a height of about 50 feet above the ground and over a lightly wooded area when its engine decelerated to idle, the pilot later reported. The spotter later recalled hearing the engine surge.

Ensurring the throttle was fully open (which it was), the pilot quickly diagnosed the situation as a genuine emergency and flew the helicopter towards a small clearing slightly to the left of the nose in their direction of travel. While managing the forward speed and height to reach the clearing, during the forced landing the right side of the helicopter impacted a tree then landed heavily in a level attitude. All three occupants were seriously injured, and the helicopter was destroyed.

The ATSB’s investigation determined that the engine power loss was due to a leak created by a loose union on an engine reference air line. During maintenance four days prior to installing a power turbine governor, the union, which was downstream of the work completed, had not been checked for tightness. An independent inspection following the installation of the governor was probably not conducted, and document verification processes did not detect that the independent inspection had not been recorded.

“This accident highlights that maintenance activities carry risk of error and therefore independent inspections are a vital risk control,” ATSB Director Transport Safety Dr Mike Walker said.

“Inspections must be designed and conducted in a way that will capture critical issues, and visual inspections will not always be enough.”

The investigation also found that the helicopter’s cabin was not well prepared for the subsequent collision with terrain, with a range of factors exacerbating the occupants’ injuries or increasing risk. For example, the DNP required shooters and spotters to wear helmets, however helmets were not provided or used on a routine basis.

Safety issues were also identified with the ambiguous wording of a Civil Aviation Safety Authority (CASA) instrument permitting the use of harnesses, and CASA’s renewal of aerial platform shooting approvals without recurrent emergency training.

“The ATSB found that the Director of National Parks did not actively manage the risk of the aerial culling task, or effectively supervise the operation,” Dr Walker said.

“This allowed for an increase in the number of crew, a change in helicopter type and change of helicopter operator, which had all progressed without requisite risk management, exposing the crew to avoidable harm.”

Following the accident, the helicopter operator ordered an immediate fleet-wide check of the security of all flexible and rigid reference air lines in its engines and took action to ensure all crew members were aware of the risk associated with using only a harness instead of a seat belt. Additionally, the approved maintenance organisation improved the delivery of human factors training for its engineers, contracting an external provider to deliver the course.

“The Civil Aviation Safety Authority has planned action to resolve the ambiguity associated with the instrument permitting harness use, and to require operators to ensure task specialists are trained in normal and emergency procedures,” Dr Walker said.

Following the accident, the DNP suspended its aerial culling activities and in December 2019 commenced an internal review of standards of practice relating to aerial culling and personal protective equipment. The DNP has reaffirmed its requirement for the use of helmets during any future culling activities and has also undertaken a specialist aviation safety review into its aerial culling operation and is conducting an ongoing review of its risk management policy and practice.

“This investigation highlights that any organisation that requires staff to engage in high-risk aviation activities should obtain professional advice on task design, actively manage risk, and provide appropriate equipment,” Dr Walker said.

Read the final report: Engine power loss and collision with terrain, Bell 206B3 helicopter, VH-FHW, 107 km south-west of Jabiru, Northern Territory, on 21 May 2019

Unsecured insulation blanket

Key points:

  • Insulation blanket ingested into one of two outflow valves, affecting aircraft pressurisation modulation
  • Crew donned oxygen masks and conducted an emergency descent, landing uneventfully
  • Maintenance instructions did not reference the insulation blanket installation procedure

An insulation blanket likely not correctly installed during maintenance was partially ingested by an outflow valve in a Fokker 100 airliner’s pressurisation system, resulting in the crew donning oxygen masks and conducting an emergency descent.

The Fokker 100 airliner, operated by Qantas subsidiary Network Aviation Services, was in the cruise at 26,000 feet on a scheduled passenger service for QantasLink from Perth to Geraldton on 10 August 2020 when the flight crew received an excessive cabin altitude warning. In response they donned their oxygen masks and commenced an emergency descent, and manually deployed oxygen masks for the passengers.

The aircraft levelled off at 9,000 feet, where the flight crew advised the cabin crew and passengers that oxygen masks were no longer required. They opted to continue the flight to Geraldton, rather than returning to Perth to avoid a flight at low level through showers and possible turbulence, where the aircraft landed uneventfully.

An engineering inspection determined that an insulation blanket had migrated from its location and became wedged in one of the pressurisation system’s two air outflow valves, affecting the aircraft’s ability to maintain cabin pressure. The subsequent investigation determined that the insulation blanket had likely not been properly secured to the aircraft’s structure during recent heavy maintenance which included zonal inspections, allowing it to move in flight and block the outflow valve.

On the Fokker 100 aircraft, insulation blankets located in the same area as the outflow valves are subject to the varying rates of airflow required to modulate cabin pressure and, if not correctly secured, are free to move and dislodge.

“The ATSB’s investigation found that while the aircraft manufacturer's instructions detailed that during maintenance installation blankets could be removed 'as necessary', those instructions did not reference the insulation blanket installation procedure,” said ATSB acting Director Transport Safety Vik Chaudhri.

“This resulted in insulation blankets not being secured to the structure.”

In response to the incident and the ATSB’s investigation, Fokker Services has advised the ATSB that it is in the process of taking a number of steps to prevent a re-occurrence, including adding the insulation blanket removal and installation maintenance manual references to the relevant job instruction cards.

In addition, the maintenance organisation, Fokker Services Asia, issued a ‘Maintenance Notice’ highlighting the importance of securing the insulation blankets in accordance with the manufacturer’s instructions. This notice was also included as part of its maintenance inspection finalisation paperwork.

Separately, Network Aviation conducted a fleet-wide inspection of its Fokker 100 fleet which identified a number of aircraft with incorrectly installed insulation blankets.

The ATSB also contacted Virgin Australia and Alliance Airlines, which also operate Fokker 100 aircraft maintained by Fokker Services Asia, to advise them of this occurrence. Both operators conducted their own inspections for incorrectly-installed insulation blankets.

“This investigation highlights the importance of clear and consistent procedures across all aircraft maintenance documentation to avoid misinterpretation and error,” said Mr Chaudhri.

“Further, when removing a part or component, it is best practice to not assume it had been correctly installed previously. In all cases, the relevant maintenance documentation should be referred to, ensuring the part or component is being installed to the current specifications.”

Read the final report: Depressurisation involving a Fokker 100, VH-NHC, 167 km south-south-east of Geraldton Airport, Western Australia, on 10 August 2020

Engine flame-out

Key points:

  • Engine flamed out shortly after departure from Geraldton
  • Fuel flow regulator had seized due to internal gearing wear, despite being maintained within the recommended service life limits
  • Crew decided to continue flight to Perth resulting in a longer exposure to one engine inoperative flight risks compared to returning to the nearest suitable airport (Geraldton). 

A Fokker 100 airliner’s engine flame-out during climb from Geraldton during a 9 July 2019 flight to Perth highlights the range of considerations for flight crews when managing power loss in complex aircraft.

The Virgin Australia Regional Airlines-operated Fokker 100 with two flight crew, two cabin crew and 24 passengers on board was climbing through 13,000 feet when the aircraft’s left Rolls-Royce Tay engine flamed out, which an ATSB investigation subsequently determined was due to the failure of the engine’s fuel flow regulator due to component wear.

After the flame-out the flight crew elected to maintain their airspeed of 250 knots and to continue to Perth. In addition, due to a desire not to ‘strain’ the right engine, the pilot flying elected not to increase thrust from climb to maximum continuous, and/or reduce the aircraft’s speed towards the recommended single-engine climb speed of 155–170 knots. Consequently, the crew adopted a cruise level about 6,500 ft below the maximum engine-out altitude.

“Following the engine failure, the crew’s decision to continue to Perth, where the aircraft landed without further incident, resulted in a longer exposure to one engine inoperative flight risks, compared to a diversion to the nearest suitable airport, which in this case was Geraldton,” said ATSB acting Director Transport Safety Kerri Hughes.

At the time of the engine failure, the aircraft was about 41 km south‑east of Geraldton.

The investigation report notes that the crew probably assessed that the likelihood of a second engine failure was remote, but may not have fully contemplated the operational risks associated with continued single-engine flight at the lower altitude of 14,000 feet. Consequently, opportunities were missed to further mitigate operational risk via repositioning the aircraft into controlled airspace, more direct tracking to Perth and the optimisation of their glide range.

“By electing not to increase thrust on the right engine or adopt the aircraft’s recommended single-engine climb speed reduced the available climb performance of the aircraft resulting in a lower cruise altitude than the maximum available,” said Ms Hughes

“This, coupled with the decision to continue to Perth on the original indirect track, increased the duration of flight and the time that the aircraft was outside the glide range of emergency airports and controlled airspace, in the unlikely event that the second engine failed.”

The investigation found the fuel flow regulator seized due to internal gearing wear, despite being maintained within the recommended service life limits of the Rolls-Royce Tay 650-15 engine management programme.

The ATSB also identified that the failure of the fuel flow regulator resulted in engine 1 thrust variation for about 45 seconds prior to the engine flameout. That went undetected by the crew due to the effects of automation, focused attention on other cockpit tasks, and the absence of any alert prior to the engine failure.

Following this incident and a review of the global failure rate specific to the fuel flow regulator unit utilised by the Virgin Australia Fokker 100 fleet, Rolls-Royce amended the applicable component management plan revising the recommended full-life maximum overhaul interval for the fuel flow regulator down from 16,000 to 10,000 hours.

“This incident highlights that the initial indications of component failures and malfunctions may be subtle. Automation can obscure significant changes in aircraft system status, including engine health,” said Ms Hughes.

“The incident also illustrates the numerous factors to be considered when managing the initial and subsequent aspects of power loss in a complex aircraft.”

Read the final report: Engine failure involving Fokker 100, VH-FWI, 41 km south-east of Geraldton Airport, Western Australia, on 9 July 2019

Ambiguous runway lighting

Key points:

  • Displaced threshold in-place for runway works
  • Airport safety officer's car headlights were directed at reflective witches’ hats which to the pilots appeared as a row of lights across the runway
  • Pilots misidentified the aerodrome works limit line as the displaced runway threshold lights

Ambiguous temporary airport works lighting contributed to an aeromedical King Air aircraft’s tyre striking an unseen temporary runway end light when landing at Cairns Airport at night, a new ATSB investigation details.   

The Royal Flying Doctor Service (RFDS) Beechcraft King Air 200 aircraft with a pilot in command under instruction, a supervisory pilot, a flight nurse and two patients on-board, landed on Cairns Airport’s runway 15 shortly after midnight on 9 July 2020. Due to on-going night runway works, runway 15’s threshold was displaced.

During the approach, the flight crew sighted an airport safety officer’s car with its headlights directed at what appeared to be a row of lights across the runway, illuminating the displaced threshold. The aircraft passed above the row of lights and touched down beyond it. However, the aircraft had landed short of the actual displaced threshold and a tyre struck an unseen temporary runway end light.

“The ATSB found that the airport safety officer's car headlights were directed at reflective witches’ hats that marked the works limit line, which was in front of the displaced threshold,” noted ATSB Acting Director Transport Safety Kerri Hughes.

“To the flight crew, this appeared as a row of lights across the runway. As a result, the flight crew misidentified the aerodrome works limit line as the displaced runway threshold lights. The actual displaced threshold lights were also indistinguishable from the taxiway lights that remained illuminated during the approach. This resulted in a runway undershoot as the aircraft landed short of the displaced threshold.”

While the runway was closed at night for normal operations during the works, a portion of the runway was available to the RFDS with prior notice, with the runway 15 threshold temporarily displaced by 1,856 metres.

The flight crew were unaware that their aircraft had struck anything on landing with the broken temporary runway end light – which had been taped to be unidirectional to aircraft using the reciprocal runway 33 and was therefore not visible to flight crew when they landed on runway 15 – discovered later that morning by an airport safety officer. An inspection of the aircraft identified a scuff mark on the right main landing gear tyre.

“Aerodrome works can pose a hazard to aircraft, particularly where there are unusable portions of a runway and a displaced runway threshold,” noted Ms Hughes.

“Aerodrome works markings and lighting must be unambiguous and laid out in accordance with relevant standards, to minimise the likelihood of confusion for flight crew and the potential for a runway undershoot or excursion.”

The ATSB’s investigation found that works and airport safety officers did not ensure the aerodrome works lighting was arranged such that the location of the displaced threshold was unambiguous to the flight crew. In addition, Cairns Airport procedures for temporary runway works lighting and markings were inconsistent and did not ensure lighting was not confusing to pilots.

Following the incident Cairns Airport implemented a number of safety actions for the remaining runway works, including ensuring that vehicle headlights were not directed towards the active runway, and illuminating taxiway lights only after an aircraft had landed.

Read the final report: Runway undershoot involving Beechcraft B200, VH-FDO, at Cairns Airport, Queensland, on 9 July 2020

Unclear communications

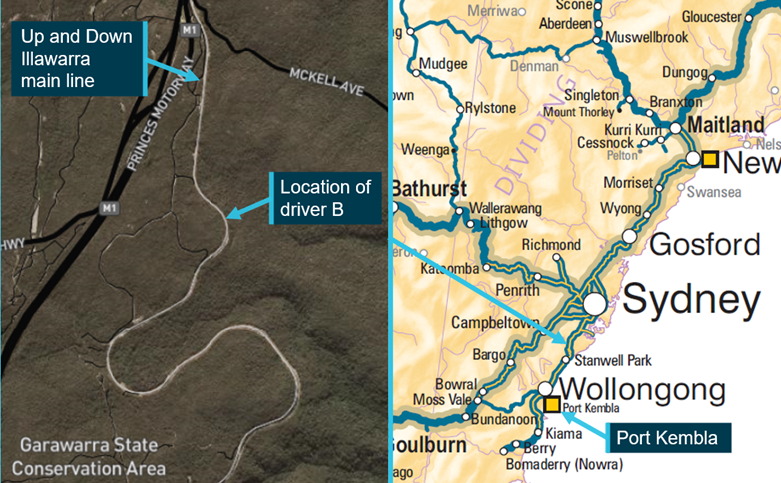
Unclear communication, confusion and misunderstanding of safeworking network rules resulted in a safeworking irregularity involving a freight train driver who unknowingly entered the track without protections in place near Waterfall, NSW, shortly after midnight on 21 August 2019, a new transport safety investigation notes.

The incident occurred while a driver was manually releasing hand brakes on Pacific National freight train 4WM2 following a remarshal* of the train consist to clear the main line due to a track fault on the adjoining network that prevented the train from travelling past signal W26U.

The remarshal involved dividing the train’s three locomotives from its rake of 50 wagons and manually securing the wagons’ hand brakes on the Up direction on the Up line near the signal. The locomotives then travelled to Helensburgh for a return journey towards Waterfall on the Up direction on the Up line to reattach the stabled wagons.

On arrival at the wagons, one of the two drivers from 4WM2 requested protections be put in place before entering the track on the Down line to reattach the locomotives and release the wagon hand brakes. During this time, a passenger train was diverted from the Up line to travel in the Up direction on the Down line to Waterfall to avoid the freight train.

As the driver released the hand brakes, the second driver on 4WM2 saw a passenger train approaching the driver on the Down line and signalled for the train to stop. The passenger train made an emergency brake application to stop before reaching the driver. There were no injuries.

A transport safety investigation into the incident conducted by the Office of Transport Safety Investigations, which undertakes rail safety investigations in New South Wales on behalf of the ATSB, established that the safeworking network rule and procedure for protecting activities associated with in-service rail traffic were not used effectively to ensure workers were protected from rail traffic.

The requests for protection were informal and did not detail the required activities or protection, the investigation notes. Both drivers of 4WM2 unknowingly entered the danger zone without appropriate protection and were at risk of being struck by rail traffic.

There were multiple parties involved in the communication and decision making relating to the movements of 4WM2, the investigation found. This led to confusion and misunderstanding of the required activities and likely affected the actions of the Waterfall Signaller and train crew. Additionally, not all communications were conducted in accordance with the network rules.

“Key lessons from this investigation are that rail infrastructure managers and rail transport operators must ensure that safety critical communication is conducted in accordance with network rules and that network controllers consider the potential dangers train crews are exposed to before requiring them to enter the danger zone, as part of a broader system to ensure the safety of workers entering the danger zone,” said OTSI Chief Investigator Dr Natalie Pelham.

“Workers must also ensure they have appropriate safeworking protection in place before entering the danger zone to protect them from rail traffic. Additionally, workers must ensure rest periods are utilised to manage non-work-related fatigue to complement rail infrastructure managers and rail transport operators’ fatigue management programs,” said Dr Pelham.

The rail operator and network owner have taken several proactive safety actions as result of the incident.

*Remarshal refers to changing the order of locomotives or wagons in a train’s consist.

Read the final report: Safeworking Irregularity, near Waterfall, New South Wales, on 21 August 2019

Out of gauge wagon

An out of gauge wagon on a freight train caused minor damage to five station platforms while travelling from Brisbane to Port Kembla, a recent ATSB investigation has found.

On the morning of 15 June 2020, wagon RKOX4055Y was unloaded at a steel facility south of Brisbane. A forklift operator had trouble unloading one of the three stacks of welded beams from the wagon, with footage from security cameras within BlueScope Steel’s Coopers Plains facility showing a corner of the wagon lifting during the unloading process before dropping back down.

With unloading completed, wagon RKOX4055Y was then shunted and attached to another 52 wagons to form Pacific National train 2BW4 for the journey to Port Kembla. Prior to departing the facility, the train underwent a full train examination and a roll-by inspection with no abnormalities detected.

At around 0430 the following morning, station staff at Grafton found damage to the station’s platform. The damage was reported to the network controller who directed the crew of 2BW4 to inspect their train on arrival at Kempsey. Another roll-by inspection was performed, however no faults were identified and the train continued its journey.

Shortly before 1100, workers at Dungog station noticed a wagon on train 2BW4 contact the platform. Network control was again advised, and the train was directed to stop at Wallarobba. On inspection, the wagon body on RKOX4055Y was found to have dislodged and was resting on the bogie.

Wagon contact damage subsequently was also found on platforms at Coffs Harbour, Taree, and Wingham.

The investigation into the occurrence, conducted on behalf of the ATSB by NSW’s Office of Transport Safety Investigations, found that during the unloading of wagon RKOX4055Y, the wagon body was likely lifted off the centre pin and dislodged as the load became stuck. The forklift operators did not notice that the wagon body had lifted and continued unloading other wagons.

During the examination of the train the underframe was not inspected as required by Pacific National’s train examination procedure, the investigation notes. The likely dislodged wagon body was not identified and train 2BW4 departed with a rolling stock irregularity.

The investigation highlights that procedures and practices for loading and unloading rolling stock must ensure risks are identified, controlled and that the practices do not affect the safe operation of rolling stock.

Further, maintenance inspection regimes must be completed in accordance with engineering practices to identify conditions that might contribute to accidents.

Following the occurrence, both BlueScope Steel and Pacific National completed several safety actions directed at preventing a reoccurrence.

Read the final report: Wagon out of gauge on freight train 2BW4, Main North rail line, New South Wales, on 16 June 2020

Importance of preparation

Key points:

  • A trainee controller’s assessment of their workload meant the pilot was not provided a requested clearance to enter controlled airspace;
  • Subsequent information provided by a second air traffic controller likely resulted in the pilot deciding to descend the aircraft, despite the pilot having other safe options to transit the area or to turn back;
  • Pilot most likely had not obtained required weather forecasts, and the aircraft was descended toward high terrain in visibility conditions below that required for visual flight.

The controlled flight into terrain accident of a Mooney light aircraft near Coffs Harbour in which the pilot and passenger lost their lives highlights both the importance of pre-flight planning and pilot proficiency checks, and the influence air traffic control can have on pilot decision-making, a new ATSB investigation details.

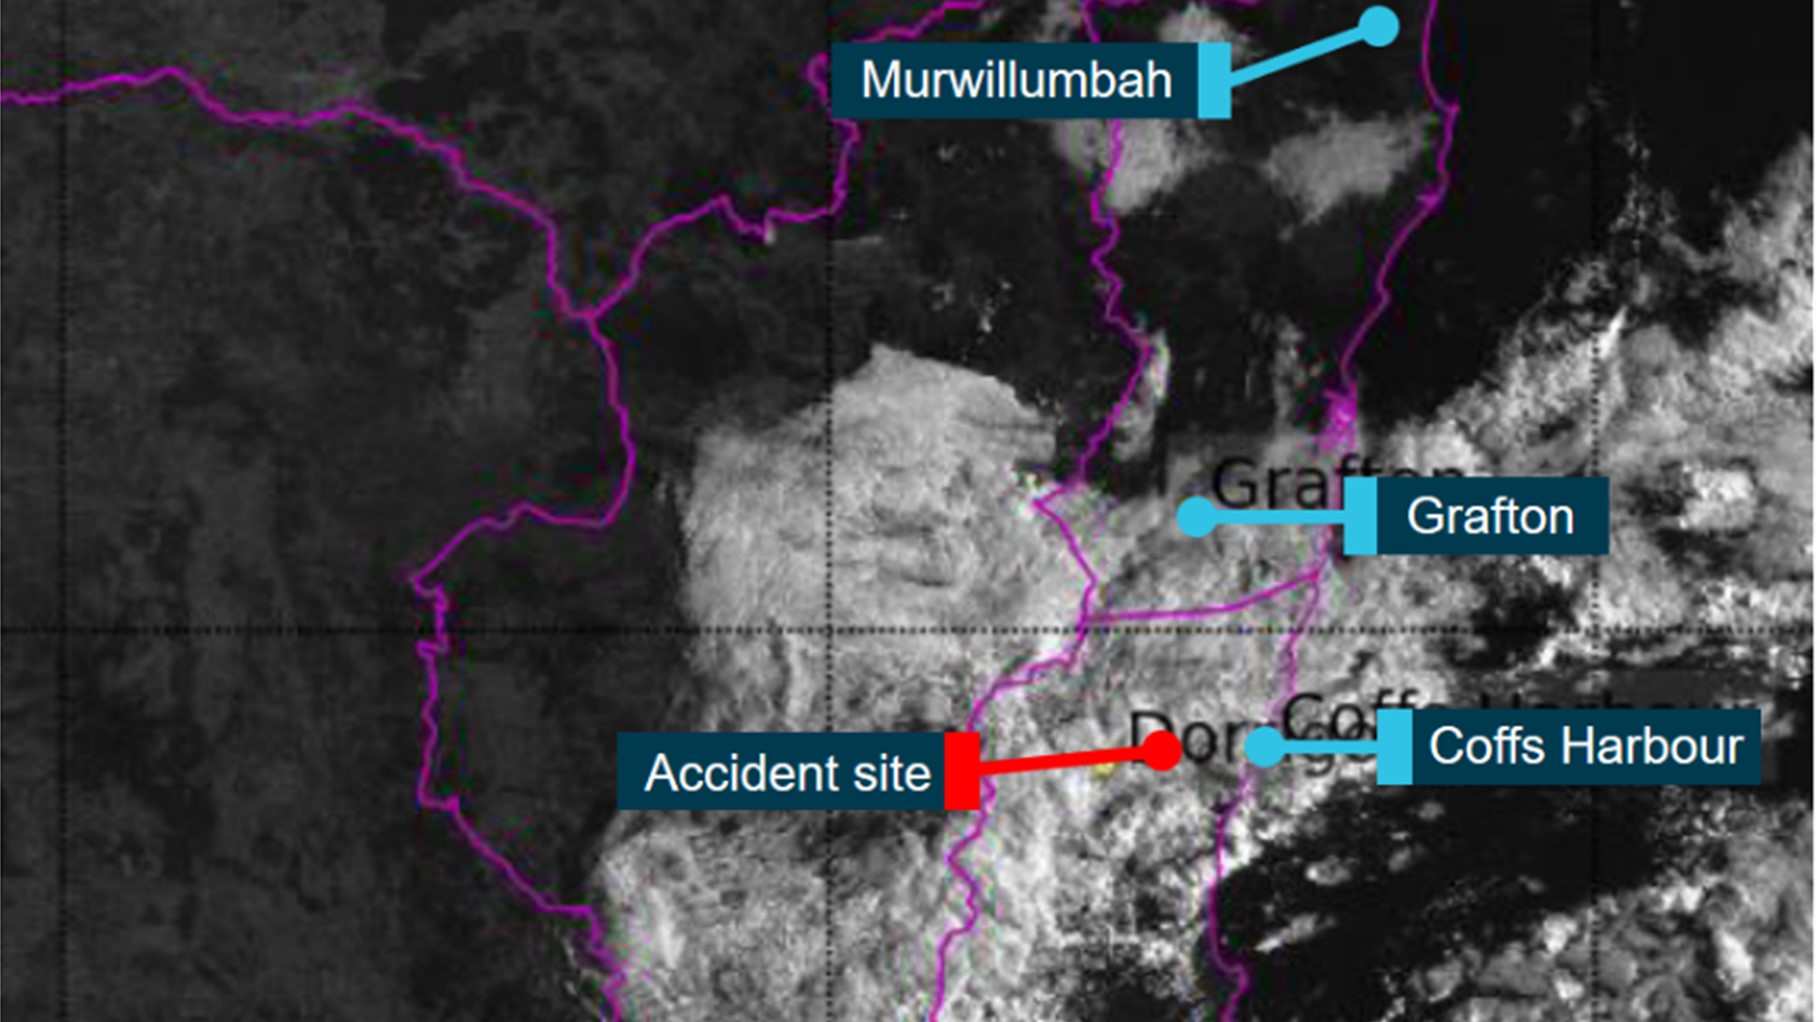
The Mooney M20J four-seat aircraft, with the pilot and a single passenger on board, was being operated on a private flight under visual flight rules from Murwillumbah to Taree on the morning of 20 September 2019. About 45 nautical miles north of Coffs Harbour at 0717 and at an altitude of 6,500 feet the pilot requested air traffic control permission to enter and transit Class C controlled airspace*, which lay in the direct track to Taree. A trainee controller working under supervision (operating from the Brisbane Centre air traffic control facility), having made an assessment of their workload, advised that a clearance was not available and provided the pilot the option to request a clearance to transit through the lower Class D airspace surrounding Coffs Harbour Airport.

The pilot subsequently contacted the controller in the Coffs Harbour control tower responsible for managing the Class D airspace, who advised that due to extensive cloud cover, a visual transit would only be possible at an altitude not above 1,000 feet. The pilot responded that the aircraft would descend to ‘not above 1,000 feet’.

The Mooney then continued on a direct track to Taree and at 0724 the pilot reported that the aircraft was operating outside controlled airspace in clear conditions at 4,100 feet and would remain on that track. Recorded air traffic control surveillance data (the aircraft was equipped with an ADS-B transponder) showed that the aircraft was then climbed to 4,500 feet before a descent was commenced, at 0732, in the vicinity of high terrain. The aircraft’s last recorded position was descending through an altitude of 3,564 feet at a ground speed of 165 knots.

When the aircraft did not arrive at Taree as expected a search was initiated. The aircraft was subsequently found to have impacted heavily wooded, steep terrain in the Dorrigo National Park at an elevation of 2,920 feet, about 26 km west of Coffs Harbour Airport. Both the pilot and passenger were fatally injured.

The subsequent investigation into the accident made a number of findings concerning both pilot proficiency and pre-flight planning, and air traffic control information, said ATSB Chief Commissioner Greg Hood.

“Information provided by air traffic control likely resulted in the pilot deciding to descend the aircraft from 6,500 feet instead of other available safe options, such as proceeding around the Class C airspace at or above 6,500 feet, diverting, or descending to the north of Grafton to proceed coastal beneath the cloud layers south to Taree,” said Mr Hood.

“The ATSB also found that the pilot was not carrying suitable navigation equipment – the pilot was likely using a handheld GPS unit while air navigation charts for the area were found stowed in a flight bag – and had most likely not obtained the required weather forecasts. These factors reduced the pilot's ability to manage the flight path changes and identify the high terrain. This led to the aircraft being descended toward the high terrain in visibility conditions below that required for visual flight, resulting in controlled flight into terrain.”

The pilot had also not completed the required flight reviews or proficiency checks, Mr Hood noted. As a consequence, the pilot did not hold a valid licence to undertake the flight, and their knowledge and skills required for effective flight management and decision‑making had likely deteriorated.

“This tragic accident emphasises to pilots the importance of flight preparation and of ensuring they have completed all required training and checks,” Mr Hood noted.

“Thorough flight planning and flight reviews and proficiency checks allow pilots to develop and maintain the necessary skills to manage challenges in flight, such as inclement weather or inadvertent entry into non-visual conditions,” he said.

“Further, confirming that appropriate operational information is obtained and readily available ensures that a pilot is well prepared to anticipate in‑flight complications and successfully manage unforeseen challenges.”

The investigation also found that the pilot was not provided clearance to transit Class C airspace due to the trainee controller’s conservative assessment of their workload, although there was no conflicting traffic, meteorological factors or limiting air traffic control instructions or procedures that would have precluded providing the clearance.

The trainee’s supervisor accepted the assessment as an alternate option – transiting through Coffs Harbour Class D airspace – was provided to the pilot.

“The pilot was not provided with a clearance to transit Class C airspace despite there being no limiting meteorological factors,” Mr Hood noted.

“Instead, the Class C controller provided the option to seek a clearance at a lower altitude with an increased risk of encountering poor weather.

“Further, the limited information provided by the Class D controller to enter that airspace probably led to the pilot’s decision to descend into a hazardous area instead of opting for other available safe options.”

Since the accident, Airservices Australia has implemented a number of proactive safety actions, Mr Hood noted.

This accident illustrates the significant influence that air traffic control can have on the conduct of a flight,” said Commissioner Hood.

“And it also serves as another reminder of the risks for visual flight rules pilots flying into non-visual conditions.

“As a former air traffic controller and private pilot myself, I urge all current controllers and private VFR pilots to read this thorough and illuminating report. It contains pertinent lessons that others can learn from.”

* Note to media – information on the classification and management of airspace in Australia can be found on the Airservices Australia website here(Opens in a new tab/window).

Read the final report: Controlled flight into terrain involving Mooney M20J, VH-DJU, 26 km west of Coffs Harbour Airport, New South Wales, on 20 September 2019

Rollingstock inspection improvements

Key points:

  • Rolling stock derailed then separated, coming to a stop near Glenalta
  • The ATSB found a pre-existing structural crack was the genesis of the derailing sequence
  • This accident highlights the importance of rolling stock managers to identify, monitor and maintain key structural risk areas of rollingstock

Rolling stock managers at Pacific National have revised their maintenance and inspection procedures and engaged an independent consultant to review repair methodology after a structural crack in the underframe of a wagon resulted in a derailment.

On 20–21 April 2018, a Pacific National freight train was travelling from Melbourne via Adelaide to Perth. A short time after commencing the downhill grade from Mount Lofty to Belair, South Australia, the train derailed and eventually separated before both portions of the train came to a stop near Glenalta.

The ATSB found that a pre-existing structural crack in the underframe of a wagon likely expanded due to in-train forces, causing the platform’s deck to bend and change angle. As the train negotiated a series of tight curves on the descending grade, a combination of wheel unloading and increased lateral forces resulted in derailment.

The ATSB found that multiple train examinations and maintenance inspections did not identify the crack, nor did Pacific National’s inspection processes identify key structural points for inspection on wagons of the type that failed.

“This incident highlights the importance of rolling stock managers considering the key structural risk areas of their rollingstock and establishing guidance methods for ensuring that these risk areas are given an appropriate level of priority when undertaking inspections,” said ATSB Director Transport Safety Dr Mike Walker.

As a result of the investigation, Pacific National altered its inspection and maintenance procedures to ensure that similar wagon types are less susceptible to this type of underframe failure, and that where detected, such cracks can be repaired.

Read the report: Derailment of freight train 6MP4, near Glenalta, South Australia, on 21 April 2018

Undetected empty wagon

Key points: 

  • Empty wagon positioned between two loaded wagons entered rail network and derailed.
  • Derailed train continued with wagon bogie dragging on the down rail of the up main line and within the six foot and foul of the down main line.
  • Lead locomotive of freight train travelling on down main line collided with bogie.

A coal train collided with a wagon bogie that had been dragged across the track by another coal train following the earlier derailment and ejection of the bogie’s wheelset from an empty wagon, a new ATSB report says.

Early on the morning of 26 September 2018, train MR336 had been loaded with coal at the Moolarben loading terminal in New South Wales. During loading, a ‘wagon empty detected’ alert was triggered but the Train Loading Officer (TLO) was unable to confirm if the wagon was loaded.

A ‘wagon empty alert’ was also triggered as the train passed over the weighbridge. Unable to visually confirm if the wagon was loaded, the TLO requested the Coal Handling Preparation Plan (CHPP) Supervisor check the 28th wagon. The supervisor and technician drove to the front of the loading train, counted back from the first wagon, and confirmed that the 27th, 28th and 29th wagons were loaded. Loading was complete and the train advised to depart.

 At about 160 km from the terminal, the leading wheelset of the trailing bogie of the 25th wagon derailed on the up main line at Antiene. The wheelset ejected from the bogie and came to a rest about 3 kms up the track. The train continued in a derailed state for 9 km, dragging the bogie across the down track until it collided with the lead locomotive of train WC915, which was travelling in the opposite direction.

The collision resulted in WC915’s lead locomotive and two wagons derailing and the 25th, 26th and 27th wagon of MR336 tipping on their sides away from the down line. There were no injuries to the drivers on either train.

A transport safety investigation into the incident by the Office of Transport Safety Investigations (OTSI), which undertakes rail safety investigations in NSW on behalf of the ATSB, established that the wheelset derailed due to an empty wagon positioned between two loaded wagons being allowed to enter the rail network.

OTSI Acting Chief Investigator Mick Quinn said empty or light loaded wagons positioned between loaded wagons running on the rail network is a known risk that can have severe consequences.

“In this instance, trailing in-train longitudinal forces lifted the empty wagon and its trailing bogie, resulting in the leading wheelset of the trailing bogie mounting the rail and dismounting in a derailed state. The wheelset then ejected from the bogie and the train continued with the bogie dragging on the down rail of the up main line within the six foot and foul of the down main line,” said Mr Quinn.

The investigation found the 25th wagon of MR336 was not loaded due to a malfunction of a ‘stop loading sensor’ in the automatic loading system being commissioned at the terminal.

“Reduced confidence in the alarm from several false empty wagon alerts during the commission process meant the TLO was pre-occupied when the alarm sounded and the opportunity to see and confirm the wagon was loaded was missed,” Mr Quinn noted.

“Other opportunities to check the wagon were also missed due to low light conditions at the terminal and the CHPP supervisor check requested by the TLO based on a check of the wrong wagon.

“This investigation highlights the need for coal loading terminals and rolling stock operators to review their processes to prevent empty or lightly loaded wagons being positioned between loaded wagons and entering the rail network.”

In response to the incident the Moolarben loading terminal corrected the malfunctioning sensor and implemented a more detailed verification process to ensure both the TLO and Control Room Operators verify trains are loaded within their specifications before advising train operators loading is complete.

A review of the terminal's risk assessment for additional train loading has implemented several actions including empty wagon detection by two independent methods, improvements in lighting, and increased monitoring of weighbridge performance. A review and update of training the train loading manual and training package has also been conducted.

Read the final report: Derailment and collision between coal trains, Ravenan (25 km from Muswellbrook), New South Wales, on 26 September 2018