Fuel data input error

Key points:

  • First officer incorrectly calculated the total fuel on board to be about 340 kg more than the actual quantity;
  • Aircraft departed Tamworth with inaccurate load, take-off and fuel management data;
  • Occurrence highlights importance of adhering to standard operating procedures, as well as clear and concise communication, and independent cross checks between pilots.

The Australian Transport Safety Bureau is emphasising the need for adherence to standard operating procedures, after a Dash 8 turboprop airliner departed with incorrect take-off data when a fuel miscalculation was not detected in pre-flight checks.

On 15 January 2021, a QantasLink Dash-8-315 aircraft had landed at Tamworth, New South Wales, and was being prepared for a return to Sydney with two flight crew, two cabin crew, and 29 passengers on board.

In the Dash-8-315, the quantities displayed on fuel tank gauges for Tank 1 and Tank 2 must be manually added together by the flight crew to get a total fuel reading.

While finalising records for the flight which had just been completed, the first officer incorrectly calculated the total fuel on board to be about 340 kg more than the actual quantity.

This error was not detected by the captain during cross checks, and the inaccurate flight record was submitted electronically.

Moving on to pre-flight procedure for the return trip to Sydney, the flight crew then relied on this incorrect mental model of the aircraft’s fuel state, rather than physically verifying the fuel quantity once again.

While going through the ‘before start’ checklist with the first officer, the captain recalled looking at the fuel gauges for the fuel quantity check, but again relied on memory to read out the fuel figure.

This resulted in the aircraft departing Tamworth with inaccurate load, take-off and fuel management data. The error was not detected by the flight crew until the aircraft reached cruise level, when it was corrected, and the flight continued without further incident.

“Thankfully, the data input error did not result in any abnormality during take-off or climb in this case,” ATSB Director Transport Safety Stuart Macleod said.

“But it is a lesson in the importance of adhering to standard operating procedures, as well as clear and concise communication, and independent cross checks between pilots.”

Data input error is one of the ATSB’s eight ‘most wanted’ safety concerns, as part of the SafetyWatch initiative.

“Flight crews can guard against errors by applying effective threat and error management strategies that recognise when such threats may arise and put in place suitable actions to minimise error potential,” Mr Macleod said.

Following the incident, QantasLink provided internal communications to flight crew on checklist usage and cross checking of data. QantasLink also intends using the incident as a case study in its human factors/non-technical skills training program.

Read the final report: Fuel data occurrence involving Bombardier Dash-8-315, VH-TQE, Tamworth Regional Airport, New South Wales, on 15 January 2021

Winch training incident

Key points:

  • Rescue crewman lost footing on deck of sea rescue vessel during helicopter winching exercise, interrupting the normal winching sequence flow;
  • The pilot reacted to a verbal communication from the winch operator and instinctively moved the helicopter away from the vessel, dragging the rescue crewman overboard.
  • Incident highlights the importance of effective communication between pilots and crewmen when undertaking winching.

A police air wing operator has taken a range of safety actions in response to a helicopter winch training incident where a crewman was dragged overboard and briefly pulled through the water, an Australian Transport Safety Bureau investigation notes.

During a 29 September 2020 training exercise, a pilot, four tactical flight officers (TFOs) and a TFO instructor on board a Western Australia Police Air Wing Eurocopter AS365 Dauphin helicopter were conducting winching to a sea rescue vessel in waters off the Perth coastal suburb of Swanbourne.

During one exercise phase, a TFO performing the role of rescue crewman lost their footing on the deck of the vessel as it pitched and travelled over a wave, just as winching had commenced to bring them back on board the helicopter.

As the pilot began to separate the helicopter from the vessel, the winch cable became taut and the crewman was pulled overboard and dragged through the water for around six seconds.

Just prior to the crewman’s fall, the winch operator had correctly called ‘winching in’. However, seeing the crewman had fallen on the deck, the winch operator called ‘crewman has fallen’.

The pilot subsequently advised the ATSB they commenced moving the helicopter away from the vessel in response to hearing the ‘winching in’ call, expecting the usual sequence to continue as had occurred on previous occasions that day.

The pilot acknowledged this was not consistent with procedure, which was to wait until the winch operator called ‘clear to move back and left’.

In addition, once the crewman had been pulled overboard, the winch operator called for the helicopter pilot to ‘hold’, intending for the helicopter to hover over the crewman in the water, instead of announcing ‘crewman overboard’, as per the procedure. The pilot interpreted the ‘hold’ message as meaning to hold position with reference to the moving vessel, which resulted in the crewman being dragged through the water. The crewman, once winched into the helicopter, confirmed they were uninjured.

“The ATSB found that, although the winch operator communicated that the crewman had fallen, this was not recognised by the pilot, who expected the usual sequence to continue as had previously occurred on numerous occasions that day during earlier training phases,” said ATSB Director Transport Safety Dr Mike Walker.

“As a result, the pilot instinctively increased the distance between the helicopter and vessel, and the rescue crewman was dragged overboard by the winch cable.”

In addition, the ATSB found that the operator did not regularly brief or practice crewman overboard drills during vessel winching training.

This contributed to a breakdown in communication during the incident, and reduced the crew’s preparedness to respond effectively to such an event.

“Effective communication between pilots and crewmen is critical when undertaking helicopter winching as the pilot is required to safely manoeuvre the aircraft while unable to visually monitor the progress of the activity,” Dr Walker said.

“Even during highly-trained and well-rehearsed operations, human performance limitations such as expectancy and reduced attention associated with a familiar task, together with deviations from standard phraseology, can have undesired outcomes.”

Separately, and though not a factor contributing directly to this event, the ATSB found that changes to sea state limitations – i.e. the severity of sea and swell conditions – that could be allowed during training exercises had been approved without the required review by the operator’s Safety Action Group.

“The absence of that review reduced the opportunity to identify any increased risk associated with the change,” Dr Walker said.

Following an internal investigation in response to the incident, the WA Police Air Wing has introduced a range of safety actions, including amending training and pre-flight briefings to include a crewman overboard scenario, and implementing crewman overboard drills during winch simulation training.

The Police Air Wing also concluded that the inherent risk of open water vessel winching outweighed the operational benefit. Consequently, it will no longer conduct open water winching to small vessels underway. Instead, to conduct an emergency response to a small vessel, it will deploy a rescue raft while winching or helocasting* a rescue crewman to the water.

This eliminates the risk of transferring persons to small vessels underway while still maintaining the same level of rescue capability to the community when required.

* Helocasting is where a crewman jumps from the helicopter at a low altitude and speed into the water.

Read the final report: Helicopter winching incident involving Eurocopter AS365, VH-WPX, near Swanbourne, Western Australia, on 29 September 2020

Light engine collision

Key points:

  • Locomotive collided with the rear of a stationary coal train on entering a loop;
  • Locomotive was operating long end leading during route tuition for two drivers;
  • Preliminary report outlines factual information, investigation is ongoing.

Long end leading operations - where the drivers' cab is to the rear of the locomotive relative to the direction of travel - is one of a number of areas of focus of the Australian Transport Safety Bureau’s on-going investigation into the fatal collision of a locomotive with the rear of a stationary coal train at Westwood, Queensland, on 18 June 2021.

The ATSB has released a preliminary report into the accident, which details factual information from the investigation’s early evidence collection phase but does not contain analysis or findings. The report notes that the single Queensland Rail (QR) 2470 class locomotive (operating as a ‘light engine’ as no rolling stock was attached) had left Rockhampton for Bluff, operating long end leading.

Three drivers were on board the locomotive: one tutor driver and two qualified drivers undergoing route tuition (to learn the signalling, speeds and track dynamics of the route) before being qualified to operate trains between Rockhampton and Bluff. One of the drivers undergoing route tuition was performing the role of driver, the other was performing the role of co-driver, assisting the driver by observing, announcing and confirming signal aspects as they were sighted.

While the route between Rockhampton and Bluff is dual track, maintenance on the Down line to the west of Westwood meant all rail traffic in that area had to use the Up line, and the common loop at Westwood was being used to facilitate passing traffic.

As the locomotive approached Westwood on the Down line, an empty Aurizon coal train was waiting in the crossing loop, and the Network Control Officer (NCO) set the signal interlocking system to show a yellow (caution) aspect at the approach signal and a red (stop) aspect at the signal before the points to enter the Westwood common loop.

The NCO then set the points as planned from the Down line into the loop.

Analysis of the locomotive’s data logger showed a partial application of the independent brake was initiated as the locomotive entered a downhill gradient into the Westwood yard. It entered the 50 km/h turnout from the Down line to the loop at approximately 72 km/h.

In response to a SPAD (signal passed at danger) alarm the NCO made an emergency radio broadcast. There was no response from the locomotive crew.

A full independent braking application was made approximately four seconds after the locomotive entered the turnout, when it was travelling at 60 km/h. The locomotive collided with the rear of the coal train, just past the start of the crossing loop, at a speed of approximately 44 km/h.

The locomotive and the last nine wagons of the coal train sustained significant damage in the collision. The driver was fatally injured, the co-driver sustained serious injuries, and the tutor driver received minor injuries.

When operating long end leading, the structure of the locomotive and the configuration of the cabin limits vision for the train crew, and as our investigation progresses, the ATSB will review and examine the functionality and cabin ergonomics of the 2470 class locomotive for long end leading operations,” ATSB Chief Commissioner Angus Mitchell said.

“We will also review the nature and extent of the use of long end leading for main line operations, other factors that might have influenced the crew’s performance, and the risk controls in place relating to collisions and authority exceedances, such as SPADs, during long end leading operations.”

The investigation will also review change management and risk management processes applicable to the use of long end leading for route tuition and post incident procedures for managing emergencies on the network.

Since the accident, QR has suspended all mainline long end leading operations, with permitted operations for long end leading limited to shunting, turning of a locomotive, setting back and propelling movements.

Separately, the Office of the National Rail Safety Regulator issued a safety alert(Opens in a new tab/window) on 25 June 2021 that required all infrastructure managers and rolling stock operators to review the risks associated with long end leading operations by the end of July.

The ATSB will release a final report at the conclusion of the investigation.

“However, should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken,” Mr Mitchell said.

Read the preliminary report: Collision between a light engine and a coal train, at Westwood, Queensland, on 18 June 2021

Corporate Plan 2021-22

I am pleased to present the Australian Transport Safety Bureau’s (ATSB) Corporate Plan, which covers the period 2021-22 to 2024-25.

This Corporate Plan has been prepared consistent with paragraph 35(1)(b) of the Public Governance, Performance and Accountability Act 2013 and the relevant provisions of the Transport Safety Investigation Act 2003 (the TSI Act), which establishes the ATSB. The Corporate Plan is also consistent with the Minister’s revised Statement of Expectations 2021–23 (SOE) for the ATSB, as notified under Section 12AE of the TSI Act. The SOE sets out clear expectations that the ATSB’s resources be used in an efficient, effective, economical and ethical way, following best practice principles and guidelines.

I acknowledge this continues to be a time of great uncertainty for the transport industry in general, and aviation in particular. As an independent safety agency, the ATSB is continuing to apply our safety knowledge and expertise and carefully monitoring the return to safe and reliable transport operations. As an operational agency, the ATSB continues to deploy accident investigation teams where and when necessary during this pandemic.

The ATSB Commission and I acknowledge the retirement of Mr Greg Hood as Chief Commissioner and Chief Executive Officer, and sincerely thank him for his leadership, professionalism and guidance in leading the ATSB from 1 July 2016 to 30 June 2021. Mr Hood drove an innovation and transformation agenda at the ATSB during his five-year term, which saw the introduction of world-leading practices including a multi-modal teams approach to investigations, new recruitment initiatives, a tertiary partnership with RMIT University, and new technologies to support investigations. All have helped to further establish the ATSB as a global leader in transport safety investigation and we look forward to yielding the benefits resulting from these advancements over the out-years.

The Deputy Prime Minister, the Hon Barnaby Joyce MP, has appointed Mr Angus Mitchell as the new ATSB Chief Commissioner and Chief Executive Officer, commencing with the agency in early September 2021. I am looking forward to supporting Mr Mitchell in his new role.

Together, Mr Mitchell and I will work to progress the key initiatives prescribed in the 2021-23 SOE. Our immediate focus will be on the continuing rationalisation of our accommodation footprint to ensure we have highly capable technical facilities to support our operational requirements and a more dispersed workforce that will enhance our ability to deploy to transport accident sites throughout Australia.

Consistent with the SOE, the ATSB is also well placed to support the Australian Government’s responses to two inquiries with recommendations concerning the ATSB’s jurisdiction and funding. These are the government responses to the:

  • Productivity Commission’s final report on its inquiry into the National Transport Regulatory Reforms; and
  • the Senate Rural and Regional Affairs and Transport References Committee report into the policy, regulatory, taxation, administrative and funding priorities for Australian shipping.

The ATSB continues to work towards achieving its new performance measures established in the 2020-21 Corporate Plan. Through revised performance criteria, we are focused on improving our timeliness, demonstrating safety action taken in response to our investigations, ensuring our findings are defendable, and using our resources efficiently and effectively.


Colin McNamara
Acting Chief Commissioner and CEO

Publication details

Publication type Corporate Plan
Publication mode Corporate
Publication date 31/08/2021

Safeworking irregularity

A freight train driver erroneously determined their train to be clear of the track section to the rear when they supplied a release code to a network control officer, who then authorised a road-rail vehicle to enter that occupied block, an Australian Transport Safety Bureau investigation details.

The safeworking irregularity occurred on 28 July 2020 at a section of dual track used for crossing trains at Sellheim Station, North Queensland on the Mount Isa Line.

Travelling from west to east, Aurizon freight train 9261 passed over a set of points to enter the down section of track, and travelled until reaching an information sign that read: ‘Stop at this point unless holding DTC (direct traffic control) authority to Mingela’.

After stopping at the sign, the driver provided network control with a release for the previous section of track.

However, the rear wagons of the train were still foul of the crossing point, occupying the released section.

The network control officer then authorised a road-rail vehicle carrying three people to proceed through the crossing point in the opposite direction, from east to west.

The road-rail vehicle subsequently came to a stop when its driver observed the freight wagons occupying the track ahead.

The ATSB’s investigation into the incident found the advisory signs where the train stopped were 940 metres past the block limit boards at the crossing point, whereas the line allowed for train lengths of up to 1,009 metres. Train 9261 was 997 metres long.

Following noise complaints, the signs had been placed by rail infrastructure operator Queensland Rail (QR) in 2015 to prevent trains from idling too close to nearby residences while waiting for passing traffic. At that time, Aurizon did not operate trains over 940 metres, but a second operator on the line did.

“The investigation found that when installing the information signs, QR did not complete a formal infrastructure change approval process or risk assessment to consider the potential operational implications of the signs,” ATSB Director Transport Safety Dr Mike Walker said.

“The investigation also found that the train driver used the information sign as a reference point for stopping rather than cross-checking the in-cab counter readout against the train comparison length,” Dr Walker said.

The driver had set the in-cab counter when they entered the section of dual track to measure the distance travelled.

The counter’s readout, being lower than the length of the train, would have indicated to the driver that the rear wagons were not clear of the crossing point.

Subsequently, the driver erroneously provided the network control officer with a release code for the Charters Towers to Sellheim section block.”

Direct train control has limited functionality to verifying the availability of a released block, Dr Walker noted.

“Given these limitations, train crew when stopping at a directional travel station to allow other rail traffic to pass, must ensure their train is in-clear before releasing the section block to network control,” he said.

“In addition, rail infrastructure managers should carefully consider the potential for information signs to be misinterpreted by rail traffic crew, particularly if such signs contain the word ‘Stop’,” Dr Walker noted.

“This occurrence also highlights the importance of rail infrastructure managers conducting appropriate change management and risk assessment processes when introducing changes to their infrastructure.”

Following the incident, QR moved the Sellheim Station information signs approximately 134 metres east, providing about 1,060 metres between the block limit boards and the signs.

QR also started a program of works to find locations on the Mount Isa Line and other lines where inconsistencies exist between infrastructure and the information contained in route maps, signalling arrangement diagrams and the DTC software.

Read the final report: Safeworking irregularity involving train 9261, Sellheim Station, Mount Isa Line, Queensland, on 28 July 2020

Tool control

Key points

  • Engine surge and power loss occurred due to damage caused by replaceable screwdriver tip being left in the engine during maintenance;
  • Tool control is an important part of aircraft maintenance, even for seemingly insignificant components;
  • Incident is a reminder that engine failures can create unusual sounds and vibrations that can’t be easily replicated in simulator training.

An engine power loss and rejected take-off incident involving an Airbus A320 at Brisbane Airport occurred after a screwdriver tip was left inside the engine during maintenance, an Australian Transport Safety Bureau investigation notes.

On 23 October 2020, the Jetstar Airways operated A320 was departing on a scheduled passenger flight from Brisbane to Cairns.

As power was being applied for take-off, the crew felt a vibration and heard a popping noise, which rapidly grew faster and louder. At the same time, the aircraft diverged to the right of the runway centreline despite the first officer applying full left rudder pedal.

The captain immediately selected reverse thrust and brought the aircraft to a stop.

Some of the passengers onboard the aircraft, a Brisbane tower air traffic controller, and flight crew of a following aircraft reported momentarily seeing flames coming out of the right engine.

The aircraft was taxied back to the airport gate, and all passengers and crew disembarked safely.

Engineers then reported finding metallic debris in the tailpipe of the aircraft’s right engine. On disassembly, it was discovered the engine’s high-pressure compressor had sustained significant damage. A removable screwdriver tip was found in the engine’s combustion section.

The ATSB’s investigation determined the screwdriver tip had been in the engine for over 100 flights.

“The ATSB concluded the tool bit had been left in the engine after maintenance and when the engine was running, it entered the high-pressure compressor, leaving dents and nicks in numerous rotor blades and stator vanes,” said ATSB Director Transport Safety Stuart Macleod.

“At least two of these dents and nicks initiated fatigue cracks, which developed during the aircraft’s subsequent operation, and led to a blade failing during the incident flight’s take-off roll.”

The liberated blade then caused greater damage to the engine’s high pressure compressor, and the engine surged, resulting in the loss of power and the low-speed rejected take-off, said Mr Macleod.

“Tool control is an important part of maintenance processes. Small and seemingly insignificant tool components can, and have, caused significant incidents or accidents.”

Mr Macleod said the incident was also a good example of why flight crews need to be aware that the noise and vibration from an actual engine failure may be greater than, or different to, that experienced during simulator training.

“High-fidelity training devices like full motion flight simulators aim to maximise the realism of an artificial environment, but there is a limit to their ability to replicate extreme events.”

Read the final report: Engine power loss and low speed rejected take-off involving Airbus A320-232, VH-VFF, Brisbane Airport, Queensland, on 23 October 2020

Level crossing collision preliminary report

Key points:

  • A driver was fatally injured when their car collided with an express passenger train at the Kianawah Road level crossing;
  • The design of the level crossing did not meet the Australian Standard. The boom barrier did not extend to the edge of the painted median traffic island, leaving a 3.1 metre gap;
  • At the time of the accident there was no formal interface agreement to manage risk at the level crossing between the rail operator and the road manager.

Risk assessment and assurance processes are among the areas of focus of the Australian Transport Safety Bureau’s on-going investigation into a collision between a car and an express passenger train at a Brisbane level crossing earlier this year in which the car driver was fatally injured.

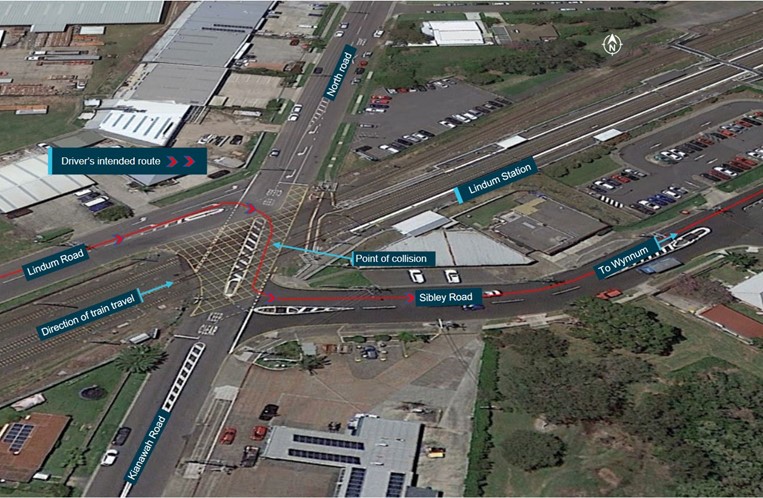
An ATSB preliminary report detailing factual information from the investigation’s early evidence collection phase notes that at around 1330 on Friday, 26 February 2021, the driver of a small four-door hatchback had left their friend’s address in Brisbane, to drive to Wynnum.

Approaching Lindum station in West Wynnum, the hatchback travelled in an easterly direction along Lindum Road, which runs roughly parallel with the Cleveland line railway before reaching a T-intersection with North Road, part of a large junction which incorporates the Kianawah Road level crossing.

The driver’s friend stated the driver, who was a resident of the Sunshine Coast, was unfamiliar with the area, and it was likely they were using a GPS navigation system.

Approaching the T-intersection, the driver’s intention was to turn right, pass through the level crossing, then turn left down Sibley Road, on the other side of the railway.

Two cars were already waiting at the stop line, also to turn right. The first turned and passed through the crossing during a pause in traffic.

At that time, around 1340, a Queensland Rail (QR) express train, travelling in an easterly direction towards Cleveland, automatically activated the level crossing protection on its approach.

The second car ahead of the hatchback turned right as the crossing’s lights were flashing, and crossed the railway as the boom gates were already lowering.

The driver of the hatchback then had to pause and give way to two other vehicles turning off North Road into Lindum Road.

The driver of the second of these vehicles observed the boom barrier was horizontal and saw a train approaching as they turned. After turning, they noticed in their rear-vision mirrors the hatchback had moved off and was approaching the crossing. They witnessed the car pass onto the level crossing and collide with the train.

CCTV footage from Lindum station showed the hatchback passed to the right of the boom barrier’s lowered arm, but to the left of the faded dotted turn guideline.

The hatchback was destroyed, and the driver, the sole occupant, was fatally injured. The train sustained minor damage and the only two occupants, the driver and guard, were not injured.

A Queensland Police Service post-accident assessment of the level crossing identified the boom barrier passed by the hatchback did not extend to the edge of the painted median island, the preliminary report notes.

The relevant Australian Standard for boom barrier design states that boom barriers shall extend to the dividing line or centre of a roadway. However, the gap between the edge of the median island and the tip of the boom barrier when lowered was 3.1 metres.

The CCTV footage showed that the boom was lowered for about 10 seconds before the hatchback passed on to the crossing.

“The ATSB is continuing to examine the risk assessments conducted for this level crossing, and the processes used for those risk assessments,” said ATSB Acting Chief Commissioner Colin McNamara.

“The investigation will also assess the assurance activities conducted by the rail infrastructure manager and the road manager relevant to risk at level crossings, including the development of an interface agreement.”

QR, the rail infrastructure manager, advised the ATSB that prior to the accident the last assessment of the Kianawah Road level crossing under the national Australian Level Crossing Assessment Model was conducted in 2002.

Separately, the preliminary report notes that Rail Safety National Law legislation requires an interface agreement between the rail infrastructure manager and the road manager be in place to outline the shared responsibility for safe railway operations at level crossings.

While this requirement had come into place in Queensland in 2012, no interface agreement had been formalised at the time of the accident.

QR has advised the ATSB that it has since formalised an interface agreement with Brisbane City Council encompassing all level crossings within the council area. Further, QR has commenced engineering activities to source and trial usage of a longer boom barrier for the northern side of the Kianawah Road level crossing. 

The rail operator and the council are also participating in the Lindum Station Precinct Study, which was initiated by the Department of Transport and Main Roads in 2019. The study is reviewing interim, short-term and long-term options for improving safety in the Lindum Station precinct.

The ATSB notes on 23 July Brisbane City Council confirmed it had already commenced work on immediate upgrades to the level cross intersection on Kianawah Road, including signalisation and reconfiguring the intersection.

Mr McNamara said the ATSB’s preliminary report does not include any safety findings or analysis, which will be detailed in the investigation’s final report.

“The ATSB’s investigation will further assess the recorded data and sequence of events leading up to the collision, along with the level crossing’s design of the and its similarity to other crossings,” he stated.

“The investigation will also further examine maintenance activity associated with the level crossing and approach roads, the history of inspections by the rail and road managers, and the history of incidents and accidents at the level crossing and connecting intersections.”

A final report will be published at the conclusion of the investigation.

Read the preliminary report: Level crossing collision between passenger train and road vehicle, Wynnum West, Queensland, on 26 February 2021

Carbon monoxide exposure

Operators and owners of piston-engine aircraft are again urged to use active warning CO detectors

co-detector-news-story.jpg

An exemplar active CO detector. Passive spot detectors have known limitations

Key points: 

  • Pilot began feeling unwell shortly after take-off, was likely exposed to elevated levels of CO; 
  • CO is an odourless, colourless gas, and may not be detected until physical symptoms and cognitive effects develop; 
  • Operators and owners of piston-engine aircraft are encouraged to use an active CO detector with active audio and visual alerts. 

The Australian Transport Safety Bureau (ATSB) is again urging operators and owners of piston-engine aircraft to use an active warning carbon monoxide detector, following the partial incapacitation of the pilot of a Piper PA-28 light aircraft near Moree last year. 

Shortly after take-off from Moree on 23 September 2020, the pilot began feeling unwell, experiencing a warm feeling in their chest, dizziness, breathlessness, some confusion and disorientation. 

The pilot then noticed a discolouration of the cabin’s disposable carbon monoxide (CO) spot detector, which rapidly darkened. They immediately returned to the airport, reduced engine power and opened all the fresh air vents and the side window. 

After a safe landing, the pilot was taken to hospital where their carboxyhaemoglobin level was recorded as being mildly elevated. The pilot was given supplemental oxygen, and began feeling better after about 2 hours. 

After the incident, engineers conducted ground runs on the aircraft, which confirmed CO was leaking into the cabin, with a new disposable CO spot detector also showing discolouration. Further inspection revealed 4-5 pinholes in the exhaust stack that were not covered properly, and unserviceable scat (air duct) hoses. Upon repairing the pinholes and replacing the scat hoses, ground runs found no indication of CO in the cabin. 

“The positive indications on two separate disposable CO spot detectors, both during the flight and during ground runs afterwards, indicated that the pilot was likely exposed to elevated levels of CO in the aircraft cabin,” said ATSB acting Director Transport Safety Kerri Hughes. 

“CO is a colourless and odourless gas, and its presence may not be detected until the physical symptoms and cognitive effects present themselves.” 

Ms Hughes noted that, while in this incident the disposable spot detector was effective in warning the pilot of the presence of CO, they do have known limitations. 

“Although commonly used in general aviation, a spot detector is a passive device that relies on the pilot regularly monitoring it for discolouration. 

“In addition, identifying a positive indication is also dependent on the detector being easily visible and accessible.” 

In 2020, the ATSB highlighted its concerns regarding exposure to CO when it issued two Safety Advisory Notices arising from its investigation into the collision with water of a DHC-2 Beaver aircraft in Jerusalem Bay, north of Sydney on 31 December 2017, in which the pilot and five passengers were fatally injured. Toxicological testing of blood samples found the pilot and two passengers had elevated levels of CO. The aircraft was fitted with a disposable CO spot detector. 

The first Safety Advisory Notice, to maintainers of piston-engine aircraft, highlighted the importance of the thorough inspection of exhaust systems and the timely repair or replacement of deteriorated components. 

The second Safety Advisory Notice, to piston-engine aircraft owners and pilots, reiterated the importance of the use of an active CO detector in the cabin.  

“The ATSB strongly encourages owners and operators of piston-engine aircraft to use a CO detector with an active warning,” said Ms Hughes. 

“These devices are inexpensive and widely available, and they provide pilots with the best opportunity to detect CO exposure before it adversely affects their ability to control the aircraft, or they become incapacitated.” 

Read the report: Partial pilot incapacitation involving Piper PA-28, VH-TBB, 19 km south-east of Moree, New South Wales, on 23 September 2020

New ATSB Chief Commissioner

The Australian Transport Safety Bureau today welcomes the Australian Government’s appointment of Angus Mitchell as the agency’s next Chief Commissioner and Chief Executive Officer.

Mr Mitchell will commence his five-year term on 2 September 2021, succeeding Greg Hood, who retired on 30 June. In the interim, ATSB Chief Operating Officer Colin McNamara will continue as the Acting Chief Commissioner.

“As the incoming Chief Commissioner I am excited to bring my 30 years’ of professional experience to help the ATSB continue to evolve as a global leader in transport safety investigation, research and analysis, and influence the implementation of positive safety action,” Mr Mitchell said.

“I have long admired and respected the quality and professionalism of the Bureau’s independent ‘no-blame’ investigation reports, and I am looking forward to helping ensure the ATSB continues as a world-leading best practice safety investigation agency which influences the national and international safety agenda.”

Mr Mitchell joins the ATSB from Maritime Safety Queensland, where as General Manager he oversaw the safe and efficient movement of vessels into and out of Queensland’s 21 ports, and was responsible for compliance activities and safety investigations for Australia’s largest recreational maritime fleet.

Maritime Safety Queensland recently was recognised with an Australian Industry and Shipping Award for its role in managing international shipping throughout the COVID pandemic and supporting the welfare and safety of international seafarers.

Prior to leading Maritime Safety Queensland, Mr Mitchell was the Executive Director of NSW Maritime, where he oversaw Australia’s largest state’s primary maritime regulatory, investigative and compliance agency. He has also served as Deputy Harbour Master – Operations for Sydney Ports, where he was responsible for managing day-to-day port operations for both Sydney Harbour and Port Botany.

Mr Mitchell also proudly served as an officer in the Royal Australian Navy for 14 years, undertaking a number of operational and policy roles.

“Angus Mitchell becomes the fourth Chief Commissioner of the ATSB, and the first with a maritime industry background,” said Acting Chief Commissioner Colin McNamara.

“We look forward to the extensive experience and expertise Angus will bring to the ATSB, and to our transport safety investigations.”

Uncommanded TOGA mode

The unplanned activation of take-off/go-around mode during the landing of a Fokker F100 highlights that flight crews can be faced with non-normal situations that require good judgement and expertise to safely manage, according to an Australian Transport Safety Bureau investigation into the incident.

On 1 September 2020, Virgin Australia Regional Airlines Fokker F100 VH-FNR was landing at West Angelas aerodrome in Western Australia’s Pilbara region, on a scheduled passenger service from Perth.

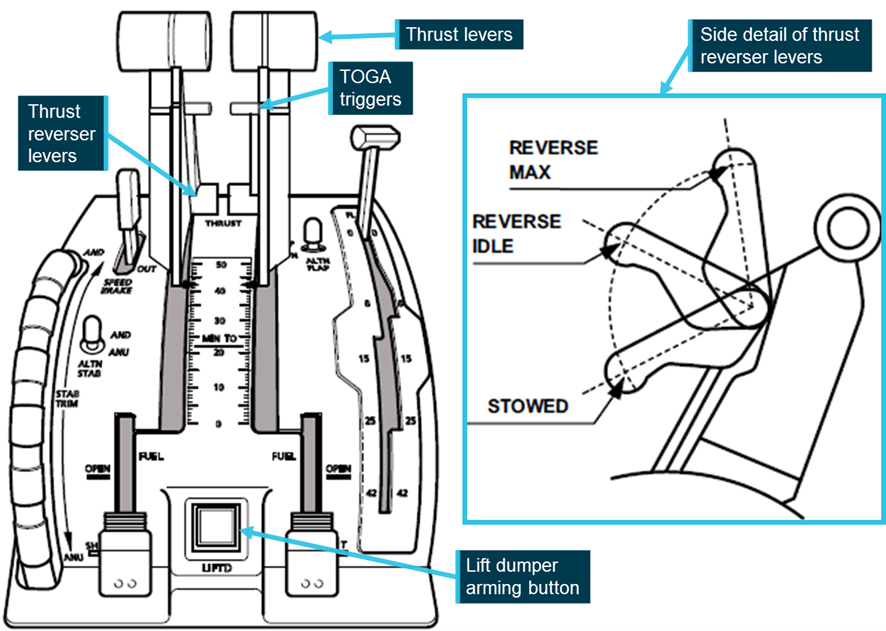
Just prior to touching down, the aircraft’s take-off/go-around (TOGA) mode activated, preventing automatic deployment of the lift dumpers to slow the landing roll.

The flight crew reported that, after touching down right wheel first, they selected the engine thrust reverser levers to the idle position, however they did not deploy. The thrust reversers were selected a second time, but again they did not deploy.

The first officer then moved the levers beyond reverse idle and applied manual braking, at which point both thrust reversers and lift dumpers deployed. The landing then proceeded as normal.

After the landing, the captain observed on the primary flight display that the go-around (GA) flight mode was active. The multi-function display unit also indicated the TOGA thrust mode.

The ATSB’s investigation into the event concluded that the TOGA mode activated for an unexplained reason, preventing automatic activation of the lift dumpers.

In addition, the weight on wheels sensors gave an intermittent signal during landing. This was most likely due to a softer than typical landing, combined with the lift-dumpers not automatically deploying due to the TOGA mode being activated.

The intermittent weight on wheels signal delayed the manual activation of the lift dumpers and deployment of reverse thrust.

“Despite the high reliability of modern flight control systems, this event highlights that flight crews can still be faced with non-normal situations that require their combined judgement and expertise to safely manage,” said ATSB Director Transport Safety Dr Stuart Godley.

“Delayed deployment of reverse thrust, lift dumpers, or a combination of the two, has contributed to runway overruns in the past.”

Under normal operation, the F100’s TOGA mode is selected by pulling two triggers located on the thrust levers. The flight crew reported the motion to actuate the triggers would be an intentional one, and they did not believe it could happen accidentally.

After the incident, maintenance engineers tested the TOGA switches, weight on wheels sensors, lift dumpers, thrust reversers, flight computers and autothrottle systems. No anomaly or unserviceability was found.

The aircraft was then returned to service, and at the time of publication there had been no reoccurrences of inadvertent TOGA mode activations.

Read the final report: Avionics system event involving Fokker F100, VH-FNR, West Angelas Aerodrome, Western Australia, on 1 September 2020