Axle friction fire

Key points:

  • A NSW TrainLink service was stopped, and the train evacuated, after a small fire was detected at the rear;
  • The fire was the result of a collapsed axle bearing, likely caused by locking plate tabs not being fitted correctly during a bogie overhaul;
  • This occurrence emphasises the significance of having adequate bearing installation processes and ensuring that axle bearings are correctly maintained and monitored throughout their operational life.

A fire which led to the evacuation of a NSW TrainLink service at Yerrinbool in the New South Wales Southern Highlands was the result of a collapsed axle bearing, likely after locking plate tabs were not fitted correctly during a bogie overhaul, a transport safety investigation notes.

The two-car Endeavour train, crewed by a driver and train guard, and with approximately 20 passengers onboard, was operating service SN68 from Moss Vale to Campbelltown on the evening of 13 October 2020.

At 1820, as the train was slowing to stop at Yerrinbool Station, the guard inside the cab at the rear of the train heard a loud noise and noticed smoke outside the window. The guard then used the train’s bell system to ask the driver to stop.

The driver brought the train to a stand at Yerrinbool Station and the passengers were evacuated onto the platform.

After receiving permission from train control to access the track the driver attempted to extinguish the fire using an on-board extinguisher, but it continued to smoulder/burn before it was put out by Fire and Rescue NSW. There were no reported injuries.

Subsequent inspection determined that parts of the axle box were heat affected and sustained significant damage to the speed sensor and rubber suspension components.

An investigation into the incident was undertaken by the Office of Transport Safety Investigations (OTSI), which conducts rail safety investigations in NSW on behalf of the Australian Transport Safety Bureau.

The investigation determined the fire was the result of a collapsed axle bearing on wheel 8 on car 2811, the last on the train.

Approximately an hour before the fire, a wayside sensor at Burradoo had detected an elevated temperature, but the detection was below the threshold for an alarm to be sent to network control.

“The investigation determined the bearing failed when the axle end cap bolts loosened and one fractured, which caused the collapse of the bearing, resulting in frictional heat, and the fire,” OTSI Chef Investigator Dr Natalie Pelham said.

“The axle bearing installation process was not sufficient to ensure the tabs on the locking plate were installed correctly during a refurbishment three months before the incident.

“It is likely that during this last overhaul, the locking plate tabs retaining the axle end cap bolts were not fitted correctly against the sides of the bolts.”

Following the occurrence, Sydney Trains – which provides maintenance for NSW TrainLink – initiated an inspection of similar axle bogies in the fleet, and undertook an audit of the practices of the contracted maintainer, United Group Limited Unipart (UGLU).

“Sydney Trains has advised improvements have been made to UGLU’s quality assurance processes to ensure bolts and locking tabs are correctly installed,” Dr Pelham said.

Sydney Trains has also implemented an improved process to review and retain UGLU’s certificate of completion checklists.

“Bearing failures continue to occur within the Australian rail network,” Dr Pelham noted.

“This occurrence emphasises the significance of having adequate bearing installation processes and ensuring that axle bearings are correctly maintained and monitored throughout their operational life.”

Read the final report: Defective axle bearing leading to fire on passenger train SN68, Yerrinbool, New South Wales, on 13 October 2020
Reduced visual cues

The pilot of a twin-engine Islander aircraft was attempting to exit south-west Tasmania’s Western Arthur Range in low visibility conditions when it collided with a ridgeline, an Australian Transport Safety Bureau investigation details.

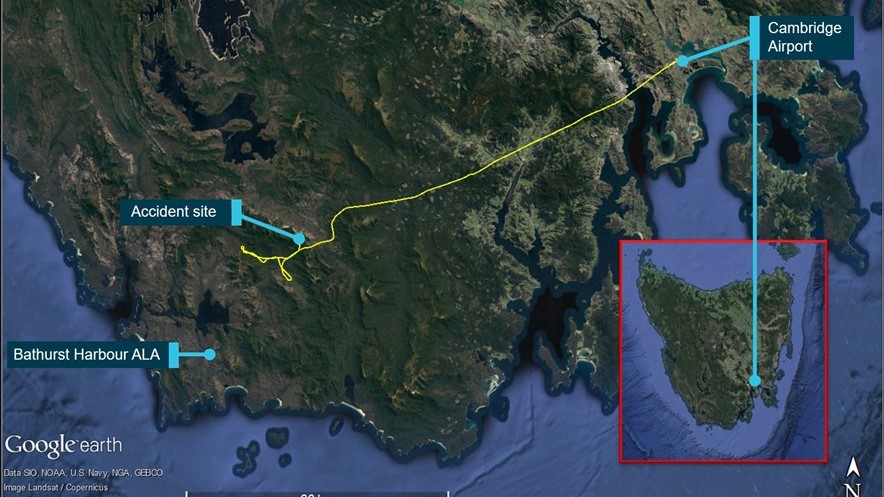
The Airlines of Tasmania-operated aircraft was conducting a positioning flight under visual flight rules on the morning of 8 December 2018 from Hobart’s Cambridge Airport to an airstrip at Bathurst Harbour in the Southwest National Park. A single pilot was on board.

Satellite-based ADS-B transponder data from the aircraft showed that the pilot had tracked from Cambridge Airport direct to Bathurst Harbour, passing through a gap (or saddle) in the Arthur Range known as ‘the portals’, a route used in low cloud conditions.

After passing through the saddle, flight data showed the aircraft manoeuvred in a valley, consistent with the pilot assessing different options for possible routes through to Bathurst Harbour, before tracking back towards the portals, the investigation’s final report details.

While in a turn under power and pilot control, the aircraft collided with a ridge on the Western Arthur Range, at an elevation of about 885 m (2,805 ft). The aircraft was destroyed in the accident and the pilot was fatally injured.

“The ATSB’s investigation found that the pilot was using a route through the Arthur Range due to low cloud and had continued over a saddle in the range at a lower altitude than previous flights along the same route,” said ATSB Director Transport Safety Dr Stuart Godley.

“During this, the pilot likely encountered reduced visual cues, and while attempting to exit the range, the aircraft collided with a ridge that formed part of the Western Arthur range,” he said.

“For pilots, this tragic accident highlights the hazards associated with flying in mountainous terrain and the need to have an escape route. It also shows the challenges of in-flight weather-related decision‑making.”

The investigation also found that Airlines of Tasmania’s guidance to its pilots for operations to Bathurst Harbour was primarily given verbally and was not well documented.

“This resulted in the operator’s pilots having varied understandings of the expectations regarding in-flight weather-related decision-making at the Arthur Range saddle,” Dr Godley said.

The ATSB’s investigation also found that, while not a contributing factor to the accident, the operator’s safety management processes had limited opportunities to proactively identify risks in all operational activities and to assess the effectiveness of risk controls.

“For operators, this investigation highlights the importance of using multiple sources to identify the hazards potentially affecting the safety of their operations, rather than relying on one key source. These can include safety occurrence reports, inspections, audits, flight data, and expert judgment,” Dr Godley said.

“Likewise, it is equally important that operators monitor and evaluate the ongoing effectiveness of existing risk controls to ensure that they remain appropriate.”

Subsequent to the accident, in January 2020, Airlines of Tasmania introduced specific guidance for its south‑west Tasmanian operations, introducing visibility requirements for pilots using the direct route through the Arthur Range saddle.

In addition, the operator added further information and guidance to its training syllabus, and introduced changes to its safety management system.

The investigation notes the operator has also committed significant resources into installing technologies to assist with flight planning and oversight of its operations. This included the installation of a new high definition 360° webcam at the Bathurst Harbour airstrip and the installation of ADS-B ground receivers at a number of locations, including within the Southwest National Park.

Another aspect of the ATSB’s investigation was an analysis of the Civil Aviation Safety Authority (CASA)’s oversight of Airlines of Tasmania, including surveillance activities. The investigation found that, while not a contributing factor to the accident, CASA’s process for acquitting repeat safety findings was not effective. While there were ongoing communications with the operator, CASA did not conduct any formal surveillance activities specifically related to the operator's safety management system.

Finally, the investigation notes that, while ADS-B transponder data provided important information to the ATSB’s investigation, the aircraft was not fitted with an onboard recording device (nor was it required to be).

“An on-board recorder would have provided valuable information to better understand the pilot’s in-flight weather-related decision-making and identify potential safety issues,” Dr Godley said.

 “The use of lightweight recorders on smaller aircraft conducting commercial passenger operations can provide a relatively simple and cost-effective way of achieving of the benefits of traditional recorders fitted to large aircraft.”

Read the final report: VFR into IMC and controlled flight into terrain involving Pilatus Britten-Norman BN2A, VH-OBL, 98 km west-south-west of Hobart Airport, Tasmania, on 8 December 2018

Rail worksite protection

A relief signaller who was working on two signal panels at once when they routed a train through a protected worksite was possibly experiencing the effects of cumulative fatigue as well as being under a high workload, a transport safety investigation report details.

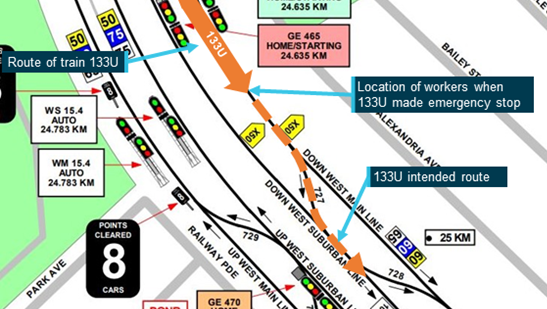
On the evening of 15 October 2019, two Sydney Trains workers and a Protection Officer (PO) were conducting track work between Parramatta and Westmead stations, in Sydney’s west. 

Absolute Signal Blocking (ASB) was being used to protect the worksite, with the PO arranging with the signaller for a pair of signals to be set to stop to prevent trains from entering the section. 

However, the signaller directed an approaching passenger train to enter the section by removing the blocking for the two signals, with the intention of routing the train through a set of points to take it onto the adjacent track, to go around the track workers.

After passing the signals, the train driver saw the workers on the track in front of them, sounded the train whistle, and applied the emergency brakes. 

The workers were able to vacate the track and danger zone, as the train came to a stop near where the workers had been. 

An investigation into the incident was undertaken by the Office of Transport Safety Investigations (OTSI), which conducts rail safety investigations in NSW on behalf of the Australian Transport Safety Bureau. 

“The investigation found the relief signaller at Granville signal box had mistakenly believed the workers were further away from the location that was provided in the agreed arrangements for Absolute Signal Blocking,” OTSI Chief Investigator Dr Natalie Pelham said.  

“This mistaken belief led to the signal protection for the worksite being removed to allow a train to go around the workers using an alternative route.” 

The signaller and the PO had discussed the need to divert trains around the worksite, but neither had correctly comprehended the implications of doing this. 

“The relief signaller was possibly experiencing the effects of cumulative fatigue due to rostering issues as well as experiencing a high workload,” Dr Pelham said. 

The rostered signaller at the Granville signal panel was absent from their workstation at the time of the incident and the relief signaller was operating both the Granville and Westmead signal panels. 

“Sydney Trains did not provide suitable management arrangements for supervision at Granville signal box to ensure there was adequate coverage on both signalling panels,” Dr Pelham said. 

“Signallers are safety critical workers who perform work which is vital to the safe performance of the rail network.  

“These workers require supervision and should be subject to suitable management arrangements to ensure compliance to relevant work instructions and requirements.” 

The relevant Network Rules and Procedures for ASB had very little direction and guidance to workers about how to manage the risk of clearing a protecting signal for an alternative route in order to run a train, the investigation notes. 

“Railway safeworking rules are in place to achieve safe rail operations and should be developed so that the desired outcomes are supported by suitable procedures,” Dr Pelham noted. 

Sydney Trains temporarily prohibited the practice of signallers being permitted to clear any signals used for ASB protection in order to run trains via an alternative route. 

Subsequent changes to the ASB rule and procedure were implemented in December 2020 to prohibit the clearing of the signal immediately protecting a worksite in order to run a train via an alternative route. 

The investigation also found there were inconsistences with Sydney Trains’ application of their fatigue management system, in particular the use of a bio-mathematical model to predict individual fatigue risk. 

Read the final report: Near hit with workers on track using Absolute Signal Blocking, Westmead, New South Wales, on 15 October 2019

Upper torso restraints

Key points:

  • A helicopter pilot conducting long-line lifting operations sustained serious head injuries during a collision with terrain;
  • ATSB investigation determined it was virtually certain the head injuries were the result of the pilot not wearing an upper torso restraint during the flight;
  • Upper torso restraints are likely not fit-for-purpose for vertical reference flying, such as long-line lifting and aerial firefighting, and are likely not routinely worn by many pilots.

Aerial firefighting and long-line lifting helicopter pilots are often subjected to an elevated risk of serious injury, as standard upper torso restraints are not suitable for use during many of these operations, an Australian Transport Safety Bureau investigation highlights.

On 17 April 2018, the pilot of a Garlick Helicopters UH-1H ‘Huey’ helicopter, was conducting long-line lifting operations near Talbingo, in the Snowy Mountains region of New South Wales, to assist drilling works for the Snowy 2.0 project.

After 11 uneventful lifting runs between a drill site and a laydown area, the pilot was climbing clear of trees near the drill site, waiting for the next load to be ready.

As the helicopter started to climb, the pilot heard a loud mechanical ‘screaming’ noise and started planning for a forced landing. Witnesses also reported seeing ‘smoke’ and some advised they heard a ‘bang’ at about the same time.

Almost immediately, the pilot also heard an audible alarm, then experienced noticeable yaw and engine power loss.

Unable to determine if ground crew would be clear of the helicopter at the drill site clearing, the pilot opted instead to conduct the forced landing in the nearby Yarrangobilly riverbed to the south-west.

The helicopter subsequently collided with trees and the riverbed, and was destroyed. Ground personnel from the drill site immediately responded to the accident, extinguishing a small fire in the engine bay and removing the pilot from the wreckage.

The pilot was wearing a lapbelt and a helmet, but was not wearing the fitted upper torso restraint.

“It was virtually certain that this lack of upper torso restraint use resulted in the pilot sustaining serious head injuries when the aircraft collided with the riverbed,” ATSB Director Transport Safety Dr Stuart Godley said.

In Australia, vertical reference flying – when a pilot looks down as well as out to position the helicopter – mainly comprises aerial firefighting, and to a lesser extent, lifting operations.

During the ATSB investigation, it was identified that a notable proportion of pilots conducting vertical reference flying operations are likely not routinely wearing upper torso restraints.

“In the majority of helicopters used for vertical reference flying, the pilot often needs to be able to lean out to look below the helicopter to observe the line and load,” Dr Godley said.

“Standard upper torso restraints are likely not fit-for-purpose for these operations. This means, in the event of an accident, the restraints cannot provide the important defence to reduce the severity of injuries.

“Engineering innovations for these restraints could reduce the risk associated with this problem, which is particularly relevant in Australia during bushfire season, when the frequency of vertical reference flying is elevated.”

During the examination of the wreckage at the site, the ATSB identified cracking and material loss visible in the exhaust diffuser area.

The helicopter’s engine was sent to the manufacturer’s facilities in the United States, where it underwent a teardown examination.

“This examination revealed extensive fatigue cracking in the exhaust diffuser inner struts, which supports the rear of the power turbine assembly,” Dr Godley said.

“When these fatigue cracks led the engine exhaust diffuser inner struts to fracture, this resulted in a complete loss of engine power.”

It was determined this high-cycle metal fatigue had not been detected for at least 34 daily, and 2 phased maintenance inspections prior to the accident.

Although the helicopter’s engine failed close to the cleared drilling area, the pilot did not have assurance that ground support personnel could vacate the drill site in an emergency.

The ATSB found that the documented risk assessment for the helicopter’s lifting operations at the drill site operations did not consider the hazard of an emergency landing.

“This increased the risk that ground personnel were not clear of the load pick-up area in the event an emergency landing was required. In this accident, this lack of assurance led the pilot to conduct the forced landing to a less suitable location, increasing the severity of impact forces during the subsequent collision with terrain,” Dr Godley said.

Read the final report: Collision with terrain, Garlick Helicopters UH-1H, VH-HUE, 24 km south-east of Talbingo, New South Wales, on 17 April 2018

Unexpected yaw

Piston engine helicopter pilots are reminded to be alert for unexpected yawing and transient reduced engine performance during flight, following an Australian Transport Safety Bureau investigation into the forced landing of a Robinson R22 near Geraldton earlier this year.

On the morning of 20 February 2021, a R22 Beta helicopter was to be repositioned from a storage depot near Geraldton Airport to Murchison House Station near Kalbarri, Western Australia.

Shortly after lifting off, at about 30-40 ft above the ground, the engine’s performance reduced, and the helicopter began to descend. The pilot completed a forced running landing in a yard adjacent to the point of departure.

“The ATSB found that an inlet valve in the engine’s number-four cylinder sustained thermal damage, which led to reduced engine performance, resulting in the forced landing,” ATSB Director Transport Safety Stuart Macleod explained.

A short time after the forced landing, the pilot elected to reposition the helicopter. However, on becoming airborne, the helicopter began to immediately rotate nose-right, and the pilot again landed the helicopter.

The ATSB investigation found that the loss of directional control was the result of a loss of drive from the helicopter’s tail rotor, due to a fracture in the tail rotor drive shaft close to its connection with the tail rotor gearbox.

“This incident serves as a reminder for all pilots of piston engine helicopters to be alert for unexpecting yawing during flight,” Mr Macleod said.

“Additionally, when a loss of engine power or abnormal operation is encountered, an appropriately licensed maintenance engineer should complete an engine cylinder inspection in accordance with the helicopter and engine manufacturer’s most recent service instructions, before any further flight takes place.”

The ATSB’s investigation also highlighted the utility of borescope inspections.

“Maintenance organisations should note that when completing a differential compression test of the engine cylinders, an accompanying borescope inspection of the cylinders and valves will provide an effective method to visually assess the condition of these components.”

Read the final report: Engine power loss and forced landing involving Robinson R22 Beta, VH-HCX, 4 km south-west of Geraldton Airport, Western Australia, on 20 February 2021

CTAF runway incursion

An incident where a SAAB 340 regional airliner crossed the holding point to enter the runway when another aircraft had commenced its take-off roll illustrates the effects expectations can have on how pilots perceive information, an Australian Transport Safety Bureau investigation report notes.

The Regional Express operated SAAB 340B, with a crew of three and 30 passengers, was being prepared to operate a flight from Carnarvon to Perth on the afternoon of 31 August 2020.

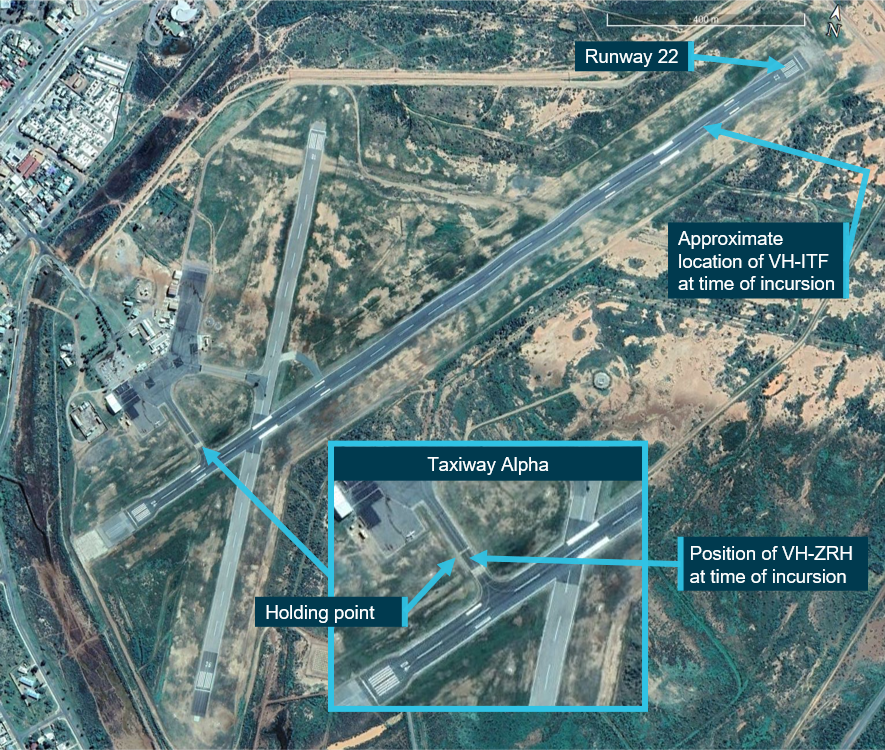
When the SAAB’s first officer was outside the aircraft conducting preflight inspections and the captain was on the flight deck, they both observed a Piper PA-31 twin-engined light aircraft taxi past them, and onto runway 22 via taxiway Alpha.

Neither SAAB pilot was monitoring Carnarvon’s local common traffic advisory frequency (CTAF) yet – nor were they required to be – so they did not hear the PA-31 pilot’s taxi call.

Carnarvon’s taxiway Alpha is at the southern end of runway 22, so aircraft are required to backtrack – taxi along the runway – before turning around and beginning their take-off roll.

Once on the runway, the PA-31, which was operating a Shine Aviation service to Geraldton with a pilot and two passengers on board, began to backtrack towards the threshold.

About three minutes after the PA-31 taxied past them, the SAAB pilots contacted Melbourne centre air traffic control to advise taxi details. Melbourne centre advised them to standby.

While waiting for Melbourne centre, the captain directed the first officer to broadcast on the CTAF that they were about to taxi.

“While the pilot of the PA-31 heard the SAAB crew’s taxi call, they did not respond on the CTAF,” ATSB Director Transport Safety Dr Michael Walker said.

“The SAAB then commenced taxiing for runway 22.”

Shortly after they commenced taxiing, the SAAB pilots were advised by Melbourne centre that the PA-31 was taxiing at Carnarvon for Geraldton and had planned the same route as them at 9,000 ft.

“However, the SAAB pilots later advised the ATSB that in their experience, air traffic control will provide the same information about another aircraft until they receive a departure call from that aircraft, which can occur some time after take-off,” Dr Walker said.

“Both pilots of the SAAB believed the PA-31 had already departed by the time they were ready to taxi, later stating they estimated at least 10 minutes had elapsed since they observed it taxiing past them.”

Based on the recorded radio transmissions, the ATSB estimated only about five minutes had passed.

“The SAAB crew said their belief the PA-31 had already departed was further enforced when they did not hear a response to their CTAF call, and did not observe any traffic on their traffic collision avoidance system (TCAS).”

When the SAAB arrived at the holding point for taxiway Alpha, the captain looked left up the runway, towards where the PA-31 was preparing to commence its take-off roll. The captain stated they did not see the other aircraft on the runway.

“At about this time, Melbourne centre passed traffic information to the PA-31, and the pilot of the PA-31 broadcast on the CTAF they had lined up and were rolling on runway 22,” Dr Walker said. “The SAAB flight crew did not hear either of these transmissions, possibly because their attention was diverted to confirming the assigned transponder code.”

Additionally, the SAAB flight crew later recalled that transmissions from the PA-31 were faint and quite scratchy, and this was supported by the aerodrome reporting officer (ARO) present during the incident.

The ATSB’s review of the CTAF recording noted the PA-31’s transmissions were distinctly weak in comparison to those from the SAAB and the ARO, but they were still audible and understandable. There was also no indication that the PA-31’s transmissions to Melbourne centre were degraded in any way.

“Since they believed the runway to be clear, the first officer of the SAAB broadcast they were entering and backtracking runway 22,” Dr Walker continued.

As the SAAB passed the holding point on taxiway Alpha, the pilot of the PA-31 commenced the take-off roll. The PA-31 pilot heard and observed the SAAB enter the runway and immediately advised them they were rolling.

The PA-31 subsequently rejected their take-off, and began backtracking again. The SAAB stopped a few metres past the holding point, prior to crossing the edge of the runway.

“This runway incursion incident highlights the potential effects that expectation can have on how a flight crew perceives information,” Dr Walker said.

“The ATSB found that although both flight crews were aware that they were mutual traffic, they both had an incorrect understanding of the other’s position and/or intentions, which led to them not recognising the potential conflict and therefore not directly communicating with each other.”

In addition, the investigation found that the lookout conducted by the SAAB’s pilots prior to entering the runway was not effective and likely to have been influenced by their expectation that the PA-31 had already departed.

Dr Walker said it is important that flight crew remain vigilant while maintaining situational awareness to counter expectation bias.

“Pilots should not hesitate to contact another aircraft if there is any uncertainty as to their position and/or intentions.”

Read the report: Runway incursion involving a SAAB 340B, VH-ZRH, Carnarvon Airport, Western Australia, on 31 August 2020

Know CO: Use an active warning carbon monoxide detector

The Australian Transport Safety Bureau (ATSB) urges operators and owners of piston-engine aircraft to know about the presence of carbon monoxide (CO) by using an active warning detector. 

CO is a colourless and odourless gas, and its presence may not be detected until the physical symptoms and cognitive effects present themselves. When inhaled, CO preferentially binds to haemoglobin, the oxygen carrying molecule in red blood cells. This creates carboxyhaemoglobin (COHb) compounds and prevents oxygen from binding to the molecule and being transported, resulting in oxygen starvation.

Symptoms can include breathlessness, confusion, disorientation and incapacitation.

Disposable chemical spot detectors, as commonly used in general aviation, may be effective in warning pilots of the presence of CO, but they have known limitations. Spot detectors are passive devices that relies on the pilot regularly monitoring it for discolouration. In addition, identifying a positive indication is also dependent on the detector being easily visible and accessible. Plus, these detectors do have a limited shelf-life when removed from their original packaging, which may be further affected by factors such as exposure to harsh direct sunlight, cleaning chemicals, and halogens. 

The ATSB highlighted its concerns regarding exposure to CO when it issued two Safety Advisory Notices arising from its investigation into the collision with water of a DHC-2 Beaver aircraft in Jerusalem Bay, north of Sydney, in which the pilot and five passengers were fatally injured. 

Toxicological testing of blood samples found the pilot and two passengers had elevated levels of CO. The levels detected were likely to have adversely affected the pilot’s ability to control the aircraft during the flight. The aircraft was fitted with a disposable chemical CO spot detector.

From the investigation, the ATSB published a Safety Advisory Notice, to piston-engine aircraft owners and pilots, reiterated the importance of the use of an active CO detector in the cabin. A second Safety Advisory Notice, to maintainers of piston-engine aircraft, highlighted the importance of the thorough inspection of exhaust systems and the timely repair or replacement of deteriorated components. 

Additionally, the Civil Aviation Safety Authority (CASA) published an Airworthiness Bulletin(Opens in a new tab/window), which encouraged operators and maintenance organisations to initiate a periodic CO detection check to measure the level of CO in the cabin at each annual or 100 hours-time in service (whichever occurs first), and each time the exhaust system or related components are disturbed.

The CO level entering the cabin must be less than 1 part in 20,000 parts of air (equivalent to 50 parts per million), derived from FAA FAR 23.83.

The ATSB's 'Know CO' campaign, launched in December 2021, encourages the use of CO detectors with an active warning. These inexpensive and widely available devices can provide pilots with the best opportunity to detect CO exposure before it adversely affects their ability to control the aircraft, or they become incapacitated.

It is worth noting that in July 2023, the UK Civil Aviation Authority (CAA) published its report into a study on how low-cost, commercial off-the-shelf, carbon monoxide CO detectors with attention-getting capabilities performed in a variety of general aviation (GA) aircraft and operating conditions.

Following a review in 2020 of accidents and incidents in the UK by the Air Accidents Investigation Board (AAIB) which identified two fatal accidents, each with two fatalities, and fifteen other events where CO may have been a causal factor over a 20-year period,  a was established to qualitatively and quantitatively investigate how low-cost active detectors perform in UK GA aircraft over a full flying season, to better understand pilot’s user experience of flying with these devices and to evaluate CO levels in a cross-section of the fleet.

Findings from the study suggested the risk of CO exposure remains a persistent background threat throughout the year and is somewhat elevated during cold weather operations. Anecdotal test evidence suggested that active CO detectors designed for domestic use can function reasonably at typical recreational GA altitudes (up to 5,000 feet). 

The report highlighted that while effective maintenance remains the first line of defence against CO and is the only way to avoid exposure, choosing to fly with an active CO detector is a decision pilots can make to protect themselves and their passengers from CO should maintenance fail.

With a wide range of active CO detectors on the market it has never been easier for pilots to find a device that suits their needs and budget. Active CO detectors are increasingly being built into other aviation equipment as standard, including ADS-B and headsets, making them ever more prevalent in GA aircraft. Additionally, some active CO detectors can be paired to personal electronic devices such as smartphones and smartwatches, increasing the likelihood of being alerted to elevated CO levels.

The report also highlighted the risk of CO poisoning may be known and understood by many pilots, the same cannot be said for consumers and third parties generally, who may fly in piston engine aircraft on a commercial or recreational basis. Pilots therefore should consider the significant safety benefits offered by flying with an active CO detector – it could not only save their life, but their passengers’ as well.

Read the report: CODE Trial Summary Report (caa.co.uk)(Opens in a new tab/window)
 

AOPA Real Pilot Story: Hidden Hazard

Flying his Mooney, Dan Bass was overcome by CO poisoning and lost consciousness while airborne. He recounts the dreadful accident and his miraculous survival waking up in a snow-covered field in the bitter north American February cold.

New Zealand Airline Academy sees immediate value of electronic CO detectors

In this CAA NZ article, The value of an electronic CO detector | aviation.govt.nz(Opens in a new tab/window), the Chief Flying Instructor of the New Zealand Airline Academy talks about Installing electronic CO detectors across its entire training fleet almost immediately saved two lives.

SPAD engineering controls

Key points:

  • A train’s driver was probably distracted by unrelated thoughts when the train passed a signal instructing it to stop;
  • Driver stopped the train across a junction about to be used by second train on hearing an emergency broadcast made by the signaller;
  • V/Line has committed to install a Track Protection and Warning System at the signal, and further signals at Southern Cross.

Victoria’s regional rail operator will install authority-overrun protection at a signal near Southern Cross station, following a near collision between two passenger trains there last year.

On the afternoon of 23 November 2020, a loco-hauled V/Line passenger train left Melbourne’s Southern Cross station for a service to Melton.

Shortly after departure, the train passed signal SST535, under the LaTrobe Street road-over-rail bridge, at about 23 km/h, despite the signal instructing the train to stop. This is known as a signal passed at danger (SPAD) event.

The train continued for about 200 m beyond the signal, before stopping across a junction which was about to be passed through by a second passenger train.

The second train, a three car V/Line VLocity train operating a Wendouree to Southern Cross service, stopped about 100 m from the junction, following an emergency broadcast from the controlling signaller.

The subsequent investigation into the near-collision, conducted on behalf of the ATSB by Victoria’s Chief Investigator Transport Safety, determined the driver was probably distracted by task-unrelated thoughts when they passed signal SST535, and probably looked past the signal to another, further along the track, which they incorrectly believed to be the signal where they were to stop.

“Once signal SST535 had been passed, the risk control to reduce the likelihood of a collision was primarily the action of the Southern Cross signaller to respond to system alarms,” Chief Investigator Chris McKeown said.

In this instance, the signaller responded by making an emergency broadcast to the Wendouree to Southern Cross service and this was sufficient to stop that train. The driver of the Melton train also overheard this broadcast and stopped their train.”

Some signals around the V/Line network are equipped with a Train Protection and Warning System (TPWS), which can automatically brake a train when a SPAD occurs.

While both trains were equipped to receive signals from a TPWS system, trackside TPWS transmitters were not fitted at signal SST535 at the time of the incident.

During a 2014 risk assessment to determine which signals on its network warranted TPWS functionality, V/Line did not consider a head-on or side-on collision to be a credible scenario as a result of a SPAD at signal SST535.

“Had a front-on or side-on collision been considered a credible scenario in the 2014 risk assessment, the risk rating of the signal probably would have led to the fitting of TPWS.”

V/Line has advised that funding was approved in July 2021 to install track-mounted TPWS transmitters at a number of signals in the Southern Cross area, including signal SST535. The operator plans to complete this installation in 2022.

Additionally, the investigation also found the absence of ‘flank-track’ protection increased the risk of a potential collision in this incident.

Where a train’s route is set over a junction, flank-track protection requires the tracks between a signal protecting a converging route and the junction to be clear before the signal will display a proceed aspect.

In this instance, flank-track protection could have directed signalling to instruct the driver of the VLocity train to stop when the SPAD occurred.

“V/Line signalling standards did not identify flank-track protection as a control to prevent collision because of a SPAD, and none was installed at the incident location,” Mr McKeown said.

“Flank-track protection was also not identified as a potential control to prevent collision because of a SPAD in the signalling standards, administered by the Rail Industry Safety and Standards Board (RISSB).”

RISSB has advised flank-track protection will be considered for inclusion when the signalling principles standard AS 7711 is next under review.

“This occurrence has highlighted the importance for passenger rail networks to have engineering controls in place to detect SPAD events and prevent potential consequences such as collision,” Mr McKeown concluded.

“In determining applicable SPAD risk controls, rail operators should consider all SPAD precursors, and potential collision scenarios.”

Read the final report: Signal SST535 passed at danger involving passenger train 8239 and near collision with another passenger train, Docklands, Melbourne, on 23 November 2020

Flight below minimum

A pilot did not conduct a missed approach on two separate occasions while on an approach to land during which their twin-engined Piper aircraft exceeded tracking tolerance limits and they lost the required visual reference with the runway while operating below the approach minima, an Australian Transport Safety Bureau investigation details.

In the early afternoon of 22 March 2021, a twin-engined PA-31P-350 Mojave aircraft was conducting a positioning flight from Dubbo to Bankstown operating under instrument flight rules, with a pilot and crew member on board.

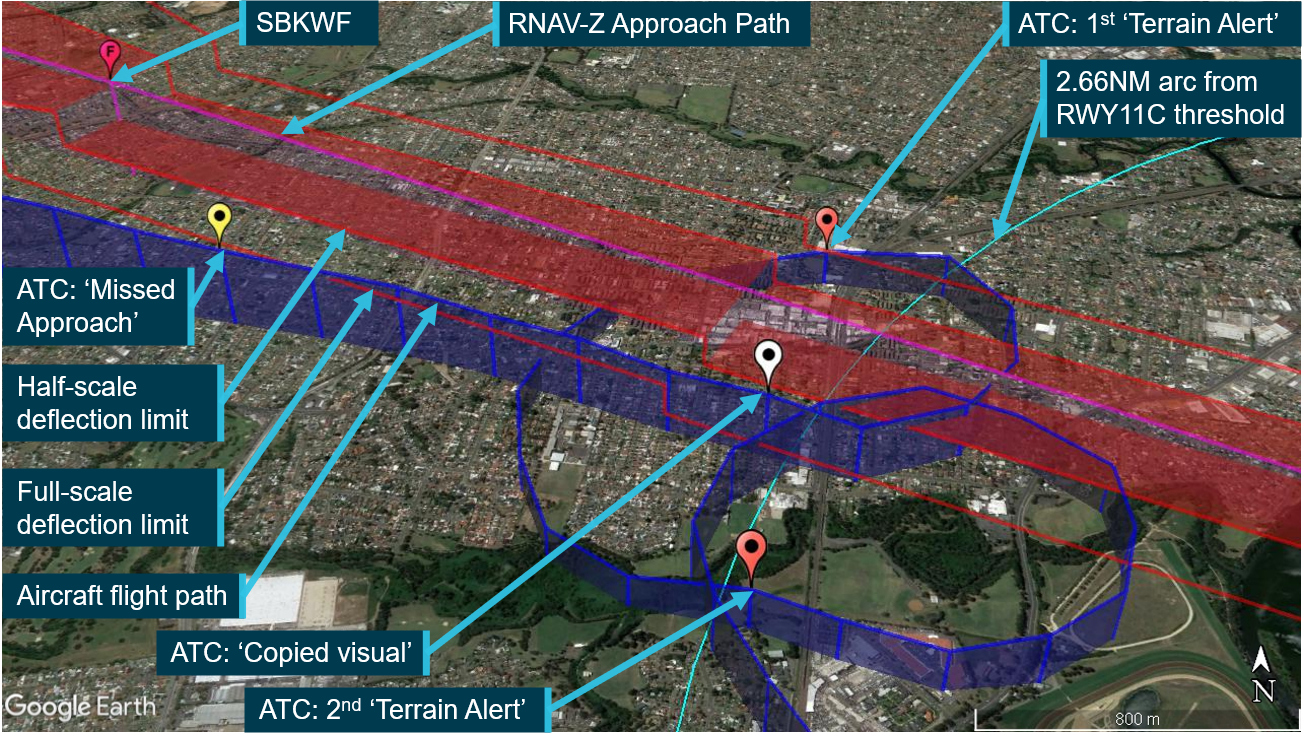
During a GPS instrument approach to Bankstown Airport’s runway 11C, the tower controller advised the pilot they were 0.5 NM south of the required track. This deviation continued as the aircraft passed the final approach fix, to the point it was exceeding tracking tolerance limits for the approach.

“The tower controller instructed the pilot to conduct a missed approach, but this did not occur,” ATSB Director Transport Safety Stuart Macleod said.

The pilot initially acknowledged that instruction but then requested, and was approved by the controller, to continue the approach visually as the aircraft had descended clear of cloud.

The pilot then conducted extensive manoeuvring, including two orbits, at low altitude and below the approach minima, that were not in accordance with the approach requirements, before landing the aircraft safely on runway 11C.

“The ATSB’s investigation into the incident found that the pilot did not conduct a missed approach when the aircraft exceeded the tracking tolerance limits, resulting in the aircraft operating significantly below the minimum allowable altitude,” Mr Macleod said.

“Additionally, having descended visually below the minimum descent altitude and commencing manoeuvring to position the aircraft for a landing, the pilot did not conduct a missed approach when the aircraft exited the circling area and the required visual reference with the runway was lost.”

Such manoeuvring was contrary to the intention of a circling approach, which is normally performed within the surveyed environment of the circuit area as part of visual circling to other than the straight‑in approach runway, Mr Macloed noted.

More importantly, when compared to the straight-in approach descent profile, it resulted in reduced obstacle clearance, increased pilot workload and an increased risk of an unstable approach.

“Adherence to operational procedures ensures consistency of pilot action and aircraft operation during the approach and landing phases of flight. This, along with careful monitoring of aircraft and approach parameters, ensures instrument approaches are conducted safely,” Mr Macleod said.

“If the criteria for safe continuation of an approach are not met, the pilot should conduct a missed approach to remove the risk of colliding with obstacles or terrain.”

Read the final report: Flight below minimum safe altitude, Piper PA-31 Mojave, VH-XGW, near Bankstown Airport, New South Wales, on 22 March 2021

Lowest safe altitude

An incident where a police air wing AW139 helicopter flew below the lowest safe altitude in the vicinity of Mount Baw Baw, Victoria, highlights the importance of lowest safe altitude calculations, according to an Australian Transport Safety Bureau (ATSB) investigation.

On the morning of 4 March 2021, the crew of a Victoria Police Air Wing AW139 was re-assigned from an aerial search near Coldstream, Victoria to a search and rescue task near Orbost. Due to cloud en route, the pilot upgraded the flight from visual to instrument flight rules.

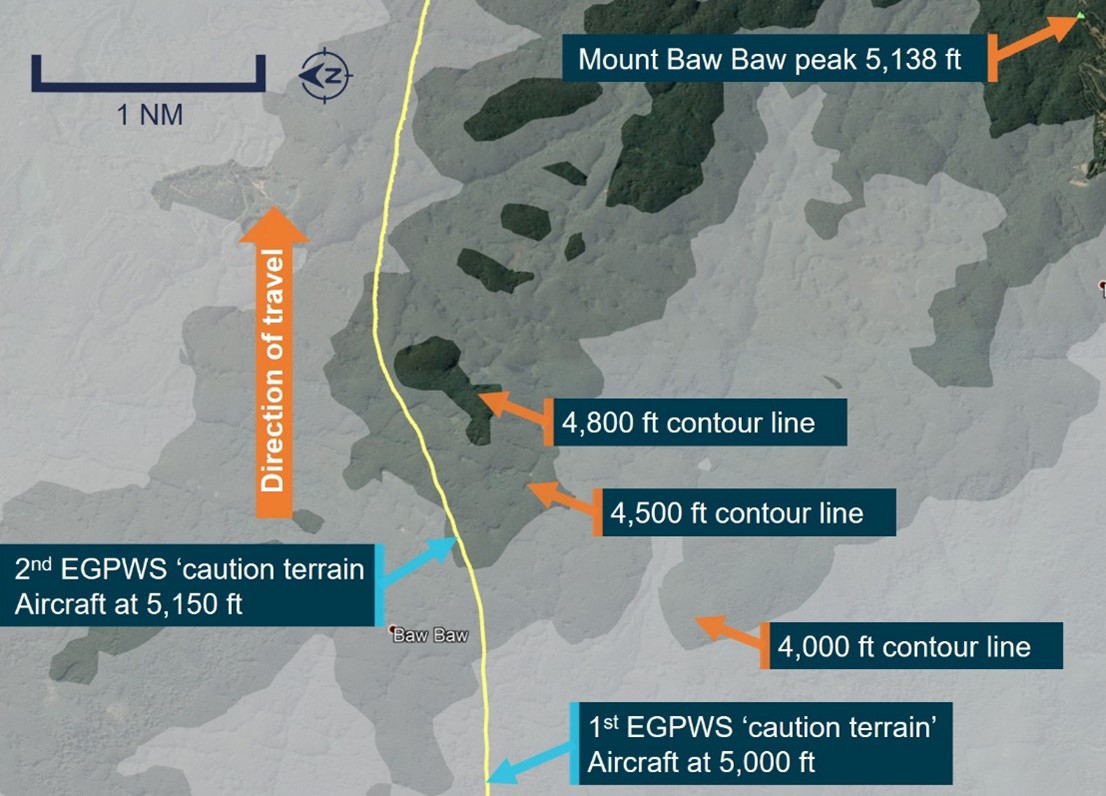
While transiting to Bairnsdale at a cruising altitude of 5,000 ft, the helicopter entered cloud and shortly after the enhanced ground proximity warning system (EGPWS) activated with a ‘caution terrain’ alert. The pilot initiated a climbing left turn to avoid Mount Baw Baw, which has a maximum elevation of 5,138 ft.

At the time of the EGPWS alert, the helicopter was about 1.8 NM (3.3 km) horizontally from and 200 ft above terrain. A few moments later during the left turn, a second EGPWS alert activated, while the helicopter was at 5,150 ft and within 0.8 NM (1.5 km) horizontally and 350 ft above terrain.

The helicopter exited cloud to the north of Mount Baw Baw and the pilot contacted air traffic control to request a climb to 6,000 ft. The flight continued to Bairnsdale without further incident.

“Lowest safe altitudes are published on aeronautical charts and in publications to ensure a minimum 1,000 ft obstacle clearance when aircraft are operating under instrument flight rules,” ATSB Director Transport Safety Dr Stuart Godley explained.

“In this incident the helicopter was below the lowest safe altitude as, based on their estimate of height above the cloud tops, the pilot had incorrectly assessed the in-flight conditions as visual meteorological conditions after the helicopter reached 5,000 ft in the vicinity of Coldstream,” he said.

“As a result, the pilot elected to remain at 5,000 ft instead of recalculating the lowest safe altitude as the flight progressed.”

Day visual meteorological conditions are an acceptable reason to operate below lowest safe altitude. As the flight progressed the pilot observed the cloud tops beginning to rise, but initially believed they would pass just over the cloud tops. However, the helicopter entered cloud just below the cloud tops while the pilot was continuing attempts to contact East Sale air traffic control.

The ATSB’s investigation found that the operator did not have a procedure for pilots for upgrading from visual to instrument flight rules when in flight.

Particularly in single-pilot operations, this would reduce the likelihood of an error when replanning in-flight, which the operator reported to be an infrequent and higher-than-normal workload task.

“Our investigation highlights the importance of lowest safe altitude calculations and to recalculate the lowest safe altitude appropriate for the area of operations,” Dr Godley said.

“Operators should also review their operations manual to ensure they have procedures in place to adequately capture their operating procedures in order to minimise the likelihood of decision‑making errors.”

Following the incident, the Victoria Police Air Wing developed an instrument flight rules upgrade procedure for inclusion in its operations manual. This procedure includes the acceptable methods for calculating lowest safe altitude and was circulated to all their pilots.

Read the final report: Flight below lowest safe altitude and ground proximity alert involving Leonardo Helicopters AW139, VH-PVO, 44 km north-north-west of Latrobe Regional Airport, Victoria, on 4 March 2021