Low-level stall

A Cessna 172 aircraft conducting powerline inspections near Canberra stalled and entered a spin at a height too low for recovery before it collided with the ground, an Australian Transport Safety Bureau investigation details.

In the early afternoon of 13 April 2021, the Cessna R172K departed Canberra Airport to conduct powerline surveying to the north of Sutton township, NSW. On board was a crew of two comprising a pilot and an observer.

About three hours into the flight, while manoeuvring to inspect a powerline adjacent to Tallagandra Lane, nearby witnesses observed the aircraft flying low above the trees before it commenced a left turn that continued into a steep descent before colliding with the ground.

The pilot and the observer were fatally injured in the accident, and the aircraft was destroyed.

During the accident flight, according to recorded data and witness accounts, the Cessna transitioned from a level, right turn to the north-north-east into a tighter, possibly climbing, left turn.

From the ATSB’s analysis of the turns conducted by the pilot earlier in the flight, it was estimated that the final turn was likely conducted at a comparatively high angle of bank and closer to the stall speed of the aircraft.

As the manoeuvre continued, the aircraft likely exceeded the critical angle of attack for the wing, causing the wing to aerodynamically stall.

“This investigation reinforces to pilots the importance of managing airspeed and bank angle to minimise the risk of stalling,” ATSB Director Transport Safety Stuart Macleod said.

“This is particularly important when operating in close proximity to the ground, such as conducting low-level air work, as well as during take-off and landing, as recovery may not be possible.”

Mr MacLeod noted the Pilot’s Operating Handbooks for most light aircraft, including the accident Cessna R172K’s, provides stall speed guidelines to avoid a wings level stall.

However, pilots should be cognisant of the raised stall speed when operating turns.

“In a bank the vertical lift component is reduced, and so pilots must pull back on the control yoke to maintain altitude,” noted Mr Macleod.

“This increases the angle of attack of the wing, and if the angle of attack reaches a critical angle, loss of lift and increased drag occurs, and the wing will aerodynamically stall.”

Following the accident, the operator amended the training and checking section of its Operations Manual to incorporate Threat and Error Management and Situational Awareness training modules for powerline low-level survey operations. The amendments enhanced existing topics in the operator’s crew resource management training and stipulated learning outcomes and assessment criteria specific to Threat and Error Management and Situational Awareness.

“The operator also provided detail of intended additions to its low-level procedures to implement an airspeed ‘manoeuvre margin’ that will take into account the increased stall speed associated with steep turns,” Mr Macleod said.

Further, the operator plans to modify its aircraft to include an angle of attack indicator and a g-meter with recording and data download capability.

“These will not only supplement the aircraft’s stall warning device by providing additional warning of an impending stall, but will allow for a record of the maximum and minimum in-flight readings to be downloaded post flight for review,” Mr Macleod said.

Read the report: Loss of control and collision with terrain involving Cessna R172K, VH-DLA, near Sutton, New South Wales, on 13 April 2021

Low-level aerobatics

Key points: 

  • Aircraft was conducting low-level aerobatics prior to colliding with water;
  • ATSB encourages witnesses, particularly those in the aviation industry, to report concerns regarding unsafe behaviour through confidential reporting channels;
  • Investigation found a pre-existing fatigue crack in the aircraft’s elevator bellcrank, although this did not contribute to the accident.

A Yak-52 warbird aircraft had been conducting low-level aerobatics at a height of less than 500 ft above the ground before it collided with water at high speed, fatally injuring the pilot and passenger, an Australian Transport Safety Bureau investigation report details.

The two-seat Yak-52, an ex-military trainer aircraft, departed Southport Airport, on Queensland’s Gold Coast, on the morning of 5 June 2019 for a private aerobatic flight expected to last about 30 minutes. The pilot had owned the aircraft since 2018, and held an endorsement to conduct aerobatics at no less than 3,000 ft above ground level.

When the aircraft did not return to Southport as planned, a search and rescue operation commenced, with part of the aircraft’s propeller located on South Stradbroke Island later that afternoon. The pilot and passenger, who had sustained fatal injuries, and additional wreckage, were recovered from the waters near Jumpinpin channel in the following days.

“The ATSB’s investigation established that prior to the accident the pilot had conducted a number of aerobatic manoeuvres below 500 ft above ground level,” ATSB Director Transport Safety Dr Stuart Godley said.

“While the absence of recorded data for the last phase of flight or witnesses to the accident meant we could not determine with certainty that the pilot was conducting an aerobatic manoeuvre immediately prior to the aircraft’s impact with the water, the ATSB considered it a possibility.”

Dr Godley said the ATSB was able to build a detailed understanding of much of the accident flight, including from air traffic control surveillance radar, which recorded an aircraft over South Stradbroke Island conducting operations with significant track and speed fluctuations, consistent with aerobatic manoeuvres, and witness reports.

Witnesses on South Stradbroke Island reported that they observed an aircraft consistent with the accident aircraft conduct a “loop, cut right, and dive below the tree line”.

“During the accident flight and previous flights, the pilot conducted low-level aerobatics without having completed the required training or having the appropriate endorsement to do so,” noted Dr Godley.

“This would have potentially limited the pilot’s appreciation of the inherent risks associated with low-level aerobatics.”

Dr Godley noted that research shows that pilot perceptions of risk may decrease with repeated successful outcomes, and if a pilot has a history of flights without incident, then they may perceive that they have a lower likelihood of an adverse outcome based on their prior incident-free experiences.

“This accident highlights the inherent risks associated with performing low-level aerobatics where there is a reduced safety margin for recovery,” Dr Godley said.

“Even more so, it demonstrates the importance of being suitably-trained and qualified to conduct these operations.”

The investigation noted that people with aviation experience and knowledge had witnessed the pilot undertake previous low-level aerobatic flights.

While there had been some attempts to communicate concerns about risk-taking behaviour to the pilot, the investigation did not find evidence that the pilot’s behaviour had been formally reported.

“We encourage witnesses, particularly those within the aviation industry, to report any concerns regarding unsafe behaviours through mechanisms such as confidential reporting systems, such as the ATSB’s own REPCON, or the Civil Aviation Safety Authority’s online reporting portal,” Dr Godley said.

“Confidential reporting provides a means to escalate concerns about pilot behaviour while providing protections for the source of the report.”

Dr Godley also noted that the investigation found a pre-existing fatigue crack in the aircraft’s elevator bellcrank, which had the potential to fail in-flight, leading to a loss of control.

Although this crack did not contribute to the accident flight, the finding prompted the ATSB in November 2020 to issue a safety advisory notice to Yak-52 maintainers and owners, emphasisng the importance of dye penetrant inspections to remove defective elevator bellcranks from service.

Read the final report: Collision with water involving Yakovlev Aircraft Factories Yak 52, VH-PAE, near South Stradbroke Island, Queensland, on 5 June 2019

Expectation bias

The runway incursion of a Beech Baron aircraft onto an occupied runway at Bankstown Airport highlights the potential effect of expectation bias and the importance of pilots focusing on specific instructions given by air traffic controllers, a new Australian Transport Safety Bureau investigation report says.

On the morning of 26 October 2021, the Baron aircraft, registered VH-NSK, and operated by Little Wings, was conducting a post-maintenance flight to test its stall warning system, the investigation report details. Prior to this flight the pilot had not conducted a VFR flight from the airport for some considerable time and had only departed Bankstown from runway 29C for flights over the last previous 18 months. 

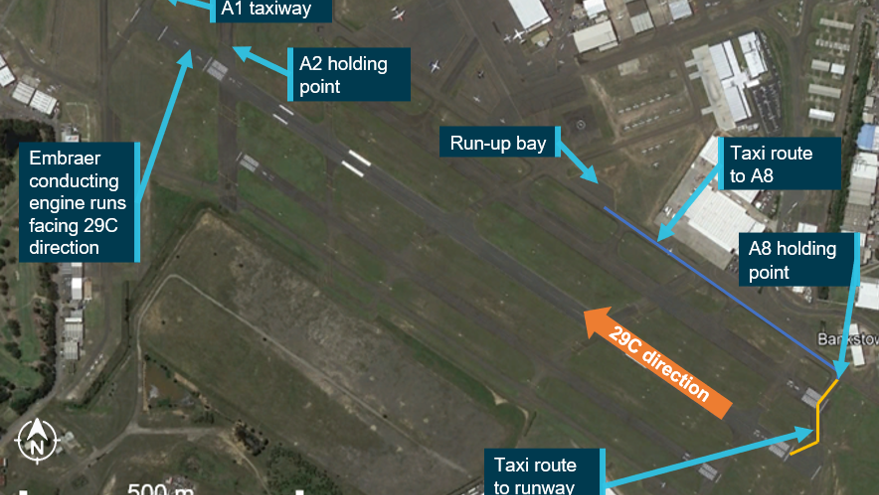
Following pre-flight checks, the aircraft was cleared to taxi to holding point A8 for a departure from runway 29R. Once there, the pilot contacted air traffic control (ATC) and advised they were holding short of runway 29R for departure and were advised to hold position. Just prior to this, an Embraer 190 received clearance to enter runway 29C at holding point A2, for high-power engine runs.

Moments later ATC instructed VH-NSK to line-up and wait for runway 29R. The pilot read back their instruction and seeing VH-NSK commence taxiing the Tower controller began assisting two helicopters operating north of the airport. During this time VH-NSK crossed runway 29R and entered and lined up on runway 29C.

Turning back to VH-NSK, the Tower controller issued an instruction for take-off.  When VH-NSK was detected on runway 29C, the Tower Controller immediately called for VH-NSK to ‘hold position, hold position you are lined up on Centre, hold position’ and issued repeated instructions to stop. At the same time, the pilot of VH-NSK saw the Embraer conducting high-power engine runs on runway 29C and did not commence the take-off.

ATSB Transport Safety Director Stuart Macleod said this incident highlights the importance of pilots focusing on the specific instructions given by air traffic controllers and how expectation bias can affect how they receive and understand verbal instructions

“As the pilot of the Baron aircraft had only conducted IFR flights departing from Bankstown’s runway 29 centre for the last 18 months it is likely their focus had narrowed to the actions for the unfamiliar VFR departure and despite confirming their instructions back to ATC they reverted to what they had done previously.

“When issued instructions by air traffic control, pilots need to focus on listening and then repeat what was said in your head and then actively apply that information,” said Mr Macleod.

For more information on runway safety and avoiding errors that lead to runway incursions go to Airservices Australia’s A pilot’s guide to Runway Safety and their specific publications for Bankstown(Opens in a new tab/window), Moorabbin(Opens in a new tab/window), Parafield(Opens in a new tab/window), Jandakot(Opens in a new tab/window) and Archerfield(Opens in a new tab/window) airports.

Read the final report: Runway incursion involving Beech Aircraft Corp. 58, VH-NSK, Bankstown Airport, New South Wales, on 26 October 2021

MH370 statement

The Australian Transport Safety Bureau has not had a formal involvement in any search for the missing aircraft MH370 since the conclusion of the first underwater search in 2017, has not recommenced a search for the aircraft, and notes that any decision to conduct further searches would be a matter for the Government of Malaysia.  

“The ATSB is aware of the work of Mr Richard Godfrey and acknowledges that he is a credible expert on the subject of MH370, but the ATSB does not have the technical expertise to, and has not been requested to, review his ‘MH370 Flight Path’ paper and workings. As such the ATSB cannot offer an assessment of the validity of Mr Godfrey’s work using WSPR data,” said ATSB Chief Commissioner Angus Mitchell.

“The ATSB does acknowledge that Mr Godfrey’s work recommends a search zone for MH370, a significant portion of which covers an area searched during the ATSB-led underwater search,” Mr Mitchell continued.

“When the ATSB was made aware that Mr Godfrey’s zone incorporates an area of ocean surveyed during the ATSB-led search, out of due diligence the ATSB requested Geoscience Australia review the data it held from the search to re-validate that no items of interest were detected in that area.”

The ATSB expects that review to be finalised in coming weeks, the results from which will be made public on the ATSB’s website.

“The ATSB acknowledges the importance of locating the aircraft to provide answers and closure to the families of those who lost loved ones,” Mr Mitchell said. “The ATSB remains an interested observer in all efforts to find the missing aircraft."

Mr Mitchell reiterated that any decision to conduct further searches for MH370 would be a matter for the Government of Malaysia, and that the ATSB was not aware of any requests to the Australian Government from Malaysia to support a new search for the missing aircraft.

Discontinuation

The Australian Transport Safety Bureau has discontinued its investigation into a light aircraft accident in which a passenger was fatally injured during a forced landing on a beach at Ball Bay, Queensland on 24 December 2021. 

 “The Australian Transport Safety Bureau conducts independent ‘no-blame’ investigations into accidents and incidents for the purpose of identifying safety issues and actions and to help prevent the occurrence of similar future accidents, and we do not investigate for the purpose of taking administrative, regulatory or criminal action,” said ATSB Chief Commissioner Angus Mitchell. 

 “In this tragic accident ATSB investigators established quite quickly that the aircraft, an amateur-built two-seat Jodel D11, was being operated outside of aviation regulations.  

“The pilot was not licenced to fly aeroplanes and the aircraft and engine had not been maintained in accordance with the appropriate regulations for about 10 years. 

“On that basis, the ATSB has determined that there was limited opportunity that continuing to direct resources at this investigation would uncover safety learnings for the broader aviation industry.” 

Mr Mitchell said investigators also determined during their examination of the aircraft wreckage that the passenger’s seat belt had completely failed at 2 locations. 

“Both the pilot and passenger’s seat belts were manufactured in May 1973 and were required to be removed from service prior to 1 January 1990 in accordance with a Civil Aviation Safety Authority airworthiness directive. 

“When owners operate outside of the rules, they remove the built-in safety defences and undetected problems are more likely to emerge,” he concluded. 

Further details on the accident flight, information determined from the ATSB’s examination of the aircraft wreckage, and the reasons for the ATSB’s discontinuation can be found on our website here. 

ATSB releases Cessna 182 collision with water near Moreton Island investigation final report

The Australian Transport Safety Bureau has released the final report from its investigation into the collision with water of a Cessna 182 light aircraft near Moreton Island. 

The Cessna 182Q aircraft had departed Caloundra Airport at around 3:30pm on 22 January 2020 for a private sightseeing flight over Moreton Island and Flinders Reef, with a pilot and passenger on- board. 

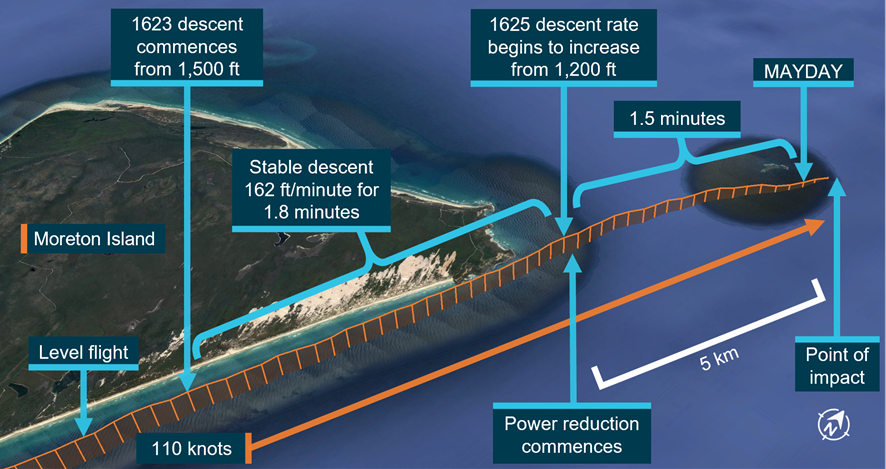
Recorded air traffic control radar data from the flight indicated that the aircraft flew along Moreton Island’s eastern coastline, from south to north, at 1,400—1,500 ft above sea level. 

The aircraft then commenced a shallow descent before passing Cape Moreton, at the northern tip of the island, at about 1,300 ft, continuing north-east towards Flinders Reef.  

The aircraft rate of descent began to increase, and after approximately 90 seconds, the pilot made a MAYDAY call that identified the aircraft’s callsign but not its position nor the nature of the emergency. 

At the time of the MAYDAY, the aircraft was east of Flinders Reef and descending through 300 ft, with a groundspeed of about 115 kt (213 km/h). The aircraft continued north-east for 15–20 seconds, before colliding with water at 4:26pm. 

On 29 January the aircraft wreckage was found on the ocean floor at a depth of about 30 m, and about 45 m from the estimated point of impact with water. The pilot and passenger were not located. 

On the evidence available, the nature of any in-flight emergency or abnormal situation, and any effect it had on the pilot’s ability to control and configure the aircraft for a ditching on the water, could not be established. 

Examination of the wreckage indicated the aircraft was likely destroyed by the collision with water at a moderately high speed and there was no evidence of pre-impact defects or structural failure. 

“ATSB investigators found that the engine’s power was reducing over the last period of the flight, for about 100 seconds,” noted ATSB Director Transport Safety Dr Mike Walker. 

At the time of the accident flight, weather conditions were conducive to carburettor icing, which is common in the region. The ice build-up within an aircraft engine’s carburettor may result in reduced power output, poor engine performance, rough running, and in extreme cases engine failure. The risk of carburettor icing is significantly increased at partial power settings (for example, when power is reduced during descent), because of the cooling effect of a partly-closed throttle. 

“The likely reduction in power in the last 100 seconds of recorded flight could plausibly have been due to carburettor icing,” Dr Walker observed.  

“However, a conclusion regarding the possible influence of carburettor icing on the development of the accident could not be drawn with any certainty. 

“Carburettor icing conditions are frequently encountered in the region, and carburettor icing can be easily prevented and managed through the use of carburettor heating.” 

During the accident flight, the aircraft maintained course away from suitable landing areas at a speed well above the aircraft’s best glide speed.  

Although the reduction in power and resulting descent would have been indicated on the aircraft’s instruments, the pilot may have been initially unaware of it because there would have been little or no change in sound and feel. 

The investigation also found that the pilot had twice descended over water beyond the glide range of a suitable landing area on a previous flight. 

“Although it could not be determined whether the aircraft’s descent out of glide range during the accident flight was intentional, pilots are reminded that the operation of single engine aircraft over water should at all times be conducted with consideration of the aircraft’s glide distance to a suitable landing area,” said Dr Walker. 

“Descending over water beyond the glide range of a suitable landing limits a pilot’s options to conduct a forced landing in the event of an emergency, such as an engine failure or partial power loss.” 

Read the final report: Collision with water involving Cessna 182, VH-WNR, 6 km north-west of Moreton Island, Queensland, on 22 January 2020

RPM governor AWB

The Australian Transport Safety Bureau (ATSB) advises all pilots, operators and maintainers of recently-built Robinson R22 and R44 helicopters to monitor for intermittent or abnormal operations of the helicopters’ engine RPM governor, which can lead to engine overspeed or underspeed conditions.

A small number of recent incidents have been reported to both the ATSB and to the Civil Aviation Safety Authority (CASA) where the governor has not controlled engine RPM under normal conditions.

“This has led to either a rotor overspeed or underspeed condition, requiring the pilot to override the governor by applying collective throttle inputs,” noted ATSB Chief Commissioner Angus Mitchell.

“The ATSB encourages all pilots, operators and maintainers of R22 and R44s purchased after 15 January 2020 to familiarise themselves with CASA’s recently-released airworthiness bulletin(Opens in a new tab/window), and to continue to report such instances via the CASA Defect Report Service portal,” he said.

“In addition, any incidents where the safety of flight is affected should also be reported directly to the ATSB.”

The engine RPM governor senses engine RPM and makes adjustments to the throttle control to maintain a constant engine RPM, which leads to a constant rotor RPM in flight, and it may not prevent over or under speed conditions during aggressive manoeuvres.

“As per the CASA AWB, pilots are encouraged to exercise care not to unintentionally override the governor by squeezing the throttle twist grip too tightly, and to monitor governor operation during flight by keeping their hand lightly on the throttle twist grip,” Mr Mitchell said.

“A properly-functioning governor will provide relatively slow, small, and frequent twist grip rotation in both directions. If twist grip rotation becomes erratic or stops altogether, the governor may be malfunctioning.”

The AWB notes that if a governor malfunction is suspected, switch the governor off, assume manual RPM control using the twist grip, land as soon as practical, and have the governor serviced by qualified maintenance personnel.

The helicopter manufacturer, Robinson Helicopter Company, is currently investigating the circumstances of the malfunctions to identify causal factors and solutions.

Banking locos runaway

Key points:

  • Two banking locomotives began to roll away from the train crew after their parking brakes failed; 
  • The two train crew boarded the locomotives but were unable to take control, and a 3 km runaway occurred before a derailment, resulting in minor injuries; 
  • Operator has subsequently modified the locomotive classes involved along with relevant procedures, and has developed resources to enable more effective training. 

A pair of banking locomotives rolled away and derailed during a change of ends at Ardglen bank in the NSW Hunter region after their parking brakes failed and the crew was unable to regain control, a transport safety investigation report details. 

On the evening of 3 June 2020, two Aurizon banking locomotives had just assisted a loaded coal train up the Ardglen bank when they came to a stop to prepare for a change of ends. 

While the two members of the train crew were transferring between the banking locomotives, the locomotives began to roll back down the Ardglen bank. The crew were able to board, but unable to take control of the locomotives. 

During the runaway event, the locomotives travelled approximately 3 km, and reached speeds of 114 km/h, before derailing and overturning on their side, and coming to a rest 13 m apart. 

The train crew sustained minor injuries in the accident and were able to exit the cabin. Both locomotives were significantly damaged, and about 100 m of track was damaged. 

An investigation into the incident was undertaken by the Office of Transport Safety Investigations (OTSI), which conducts rail safety investigations in NSW on behalf of the Australian Transport Safety Bureau. 

“During the process of changing ends, the driver likely depressed the independent brake handle accidentally, at the same time as placing the now-trailing locomotive into ‘Trail Cut-out’ mode,” OTSI Chief Investigator Dr Natalie Pelham explained.  

“This released the automatic air brake application on both locomotives.” 

The park brakes were then ineffective in holding the locomotives on the grade at Ardglen, and the banking locomotives started to roll away. 

“Rail transport operators should ensure parking brake systems on locomotives are effective, regularly inspected and maintained,” Dr Pelham said. 

The investigation found Aurizon’s relevant work instruction lacked specific detail about how to safely change ends – this information was included in the Operator’s Manual and also detailed in training documentation. 

“Without the step-by-step information being detailed in the work instruction, Aurizon’s system did not provide a clear ‘how to’ for safely changing ends,” Dr Pelham said. 

“Work instructions in quality management systems explain ‘how’ things need to be done. In this case, the work instruction detailed ‘what’ needed to be done, but the ‘how’ was left to the train crew to carry out based on what they could recall from their training.” 

The OTSI investigation also found that, during the runaway, the use of the forced lead function on the locomotives would likely have allowed the train crew to regain control, but the crew had not been trained to use this function. 

“Operators’ safety management systems should contain operational work instructions with sufficient detail on how to carry out safety critical tasks, like using the forced lead function,” Dr Pelham said. 

Since the incident, Aurizon completed an internal investigation, and commenced and completed several actions to prevent a recurrence. 

The operator completed modifications on the locomotive classes involved in the incident to improve alignment in the braking system, resulting in improved park brake force. 

It also modified the procedure clarifying steps for changing ends and when to use forced lead function and monitoring, and began monitoring the correct application of the procedure through regular analysis of locomotive downloads. 

Finally, the operator developed training resources to enable more effective training in emergency situations. 

Read the final report: Uncontrolled runaway and derailment of banking locomotives, Kankool, New South Wales, on 3 June 2020

Regulation consultation

New categories of aircraft operations, additional responsible persons, and harmonised definitions with domestic and international standards are drafted in proposed updates to Australia’s Transport Safety Investigation Regulations.

The ATSB is calling on its aviation, marine and rail stakeholders to take part in the consultation process to help shape the next update of Australia's Transport Safety Investigation (TSI) legislation.

Under the TSI Act, The TSI Regulations define what occurrences are reportable to the ATSB, how urgently they should be reported, what form a report must take, and who is responsible for making a report.

The ATSB has released an Exposure Draft and Consultation Paper detailing proposed amendments. This is towards finalising the new Regulations by mid-2022, for commencement at the start of 2023. 

The proposed changes have been prepared by the ATSB working closely with the Office of Parliamentary Counsel, and have been shaped by the ATSB’s ongoing work, a series of past consultations in 2019 and 2021, and continuous engagement with industry stakeholders.

“Broadly speaking, the proposed changes aim to bring transport safety investigation legislation in line with industry and international standards, and help the ATSB maximise its ability to improve transport safety, without placing undue burden on industry,” ATSB Chief Commissioner Angus Mitchell said.

Among the six issues discussed in the Consultation Paper is the proposed recategorisation of aircraft operations, to prioritise them in four distinct categories.

New, clear definitions for aircraft accidents and incidents would then prescribe what occurrences need to be immediately reported, or routinely reported, for each category of operation, with higher categorisations bearing a stricter reporting standard.

“The Statement of Expectations, provided to the ATSB by the Minister, makes it clear we should use our resources for the greatest public safety benefit,” Mr Mitchell said. 

“Ensuring the greatest focus is on receiving reports with the highest potential to improve safety, is in line with that directive.”

The proposed changes would also extend the persons who are responsible to report occurrences in the aviation and marine sectors.

In aviation, this would include sport aviation bodies and insurers of aircraft as responsible persons. In marine, pilotage providers and vessel traffic service authorities would be added.

“It’s important to note that, as with the existing framework, a responsible person only has to report an occurrence if they have a reasonable belief that no other responsible person has reported the matter,” Mr Mitchell noted.

“For example, if an aircraft is damaged in an incident, and the insurer receives assurance from the pilot that the occurrence has been reported, the insurer would not have to report that incident.

“But the goal of this change is to make sure that accountability is there, and ultimately reduce the number of occurrences that are not reported to the ATSB.”

One welcome proposal for all operators will be the extension of written reporting timeframes from within 72 hours to within 7 days. This will form part of a separate package of work to amend the TSI Act.

“This proposal relates to the written report, which follows the initial notification via telephone as soon as possible after an occurrence,” Mr Mitchell explained.

“Considering prior consultation and stakeholder engagement, the ATSB is of the view that a 7-day window to file a formal written report will maximise the quality of information that can be included, without sacrificing the recency necessary to ensure the information is current. If this proposal is supported by industry, we will work with government on making these changes.

“It is worth noting this will not change the existing pathways for reporting an incident to the ATSB; that is, through the Office of the National Rail Safety Regulator for rail occurrences, the Australian Maritime Safety Authority for marine occurrences, and directly to the ATSB for aviation occurrences,” Mr Mitchell added.

The Consultation Paper also explains a number of clarifications, minor and technical changes, proposed with the goal of better aligning the language of legislation to the other changes proposed in this consultation round. 

It also proposes prescribing the format for written reports, aligning with the Minister's Statement of Expectations by ensuring the ATSB can work efficiently to improve transport safety.

“I encourage all of our stakeholders to go to our website and check out the Consultation Paper and Exposure Draft for these proposed changes,” Mr Mitchell concluded.

“You can then take part in our consultation survey and give us the valuable feedback we need to finalise these changes.”

Consultation closes 7 March 2022. 

Review the Consultation Paper and other documents here.

Complete the consultation survey here(Opens in a new tab/window).

Taxiing excursion

Key points:

  • After nose wheel turning angle was unexpectedly restricted during taxiing, the captain opted to continue a turn, briefly exiting the runway area;
  • In such an unexpected event where there is sufficient time to assess available options, flight crew are encouraged to utilise all available resources to determine the safest course of action.

Flight crews should utilise all available resources when they encounter unexpected events during taxiing, an Australian Transport Safety Bureau report into a taxiing excursion by an airliner at Laverton notes.

On the afternoon of 28 September 2021, a Fokker F100 aircraft, operated by Alliance Airlines, landed uneventfully at Laverton Airport, Western Australia, following a scheduled passenger flight from Perth, with 2 flight crew, 3 cabin crew, and 75 passengers on-board.

After completing the landing roll, the captain began to taxi the aircraft towards the end of the runway, intending to turn around and backtrack to the taxiway.

Upon reaching the end of the runway, the captain commenced a right turn by rotating the nose-wheel handwheel, or tiller. However, the captain was unable to achieve full tiller rotation, even when using the force of both hands.

They attempted to tighten the turn by applying the right inboard brake, and asymmetric thrust, but this did not have the desired effect.

“A torn boot on a universal joint probably restricted the operation of the aircraft’s nose-wheel steering system, preventing the aircraft from completing the turn on the runway,” ATSB Director Transport Safety Stuart Macleod explained.

Realising the aircraft would not be able to complete the turn without the nose-wheel leaving the runway surface, the captain decided to continue.

They later reported this decision was made based on their knowledge of the ground next to the runway being compact dirt, and the fact the airport had a single runway and no ground support equipment, so stopping would prohibit other aircraft from landing.

“In continuing the turn the nose-wheel left the runway surface and entered the runway strip, increasing the risk of damage to the aircraft,” Mr Macleod said.

“While there was no damage to the aircraft, there was no assurance that the runway strip was clear of hazardous debris and could safely manoeuvre on the strip.”

Mr Macleod noted that other aircraft would have been unable to safely land if the Fokker had remained on the runway.

“But options such as having the airport staff inspect the runway strip before completing the turn onto it were available,” Mr Macleod said.

“This incident highlights that when flight crews encounter an unexpected event and there is sufficient time to assess available options, they should utilise available resources to determine the safest course of action.”

After completing the turn and re-entering the runway, the captain taxied the aircraft to the terminal without incident.

A post-flight inspection identified damaged insulation in the nose-wheel area, and the torn universal joint boot on the tiller shaft.

Read the final report: Taxiing excursion involving Fokker F100, VH-FKD, Laverton Airport, Western Australia, on 28 September 2021