Collision between suburban electric passenger train 1648 and suburban electric empty train 1025

Final report

Executive summary

At about 0914 on Tuesday 18 June 2002 a scheduled suburban electric passenger train number 1648, on an up journey, collided with an approaching scheduled suburban electric empty train number 1025, on a down journey, on a section of single line, 772.3 metres south of Epping Railway station. Passenger train 1648 had a driver and 16 passengers on board, while the empty train 1025 had a driver and two other drivers travelling as passengers with the train. Train 1025 was traversing a single line section and crossing into Epping Yard at the time of the collision. The leading cab on train 1025 had just traversed a set of points and passed the fouling point for both the main line and the crossover line into Epping Yard, moments prior to the collision. Train 1648 had departed Epping platform and was advanced into the single line section on a restricted indication, and had subsequently passed signal EPP121 that was indicating stop. Both trains and infrastructure, including signalling and tracks, were operated by Melbourne Transport Enterprises, through Connex Trains Melbourne (CTM) and Alstom Melbourne Transport Limited (AMTL).

Damaged passenger train

Emergency services, including the Police, Fire and Ambulance services attended the scene. The driver of the passenger train suffered bruising to his right upper arm, but was discharged from hospital on the day of the collision. Minor injuries to passengers were reported. No passengers were hospitalised.

The evidence available, including an expert medical assessment, suggests that the driver of train 1648's performance was impaired by his physically 'unwell' condition. He could not recall events between the departure from Epping station on the up journey and the point that the train passed signal EPP121 at stop, a period of about one minute. As a result, signal EPP121 was passed at stop and a collision occurred. Train 1648 was travelling at about 60 km/h and train 1025 at about 12 km/h, at the point of initial impact.

Signal distances at Epping
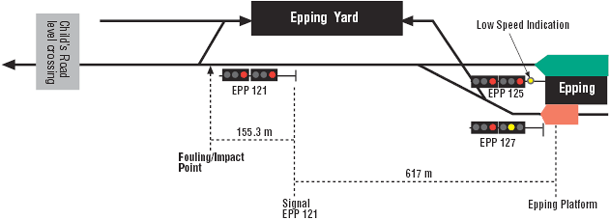
Diagram showing Epping Yard signal distances


There are safeguards or defences to protect against such an accident. On this occasion the defences in place failed to prevent the accident. A number of defences were identified as being inadequate in terms of design or application.

The investigation established that train maintenance was not a factor in the accident. In addition, the signalling system, which incorporates automatic train stops, operated within its design criteria. However, the design criteria of the signalling system was such that it could not maintain a minimum safety margin to prevent the collision, given the speed of the passenger train involved.

Trains are fitted with pilot valves (including a dead man's handle), so that in the event that a driver becomes incapacitated the train should be brought to a halt. On this occasion the driver of train 1648 had become incapacitated but the pilot valve did not activate by applying the train's emergency brakes.

The performance of the driver of train 1648 was impaired by migraine symptoms, and possibly treatment, and the effect of stressful personal circumstances. The driver's history of migraine had been declared during regular medical assessments but the medical guidelines did not address the symptoms or treatment for a potentially incapacitating illness. The report also addresses factors that contribute to the driver working when he was unwell.

The Investigation Team has also reviewed the factors surrounding the Footscray collision on 5 June 2001 (ATSB rail investigation report no. 11-01) and considers this event to contain some similar safety issues.

A number of safety actions have been taken or are underway through the Victorian Department of Infrastructure.

The report's recommendations on pages 41 and 42 relate to:

  • the design of the signalling system;
  • the train working procedures for trains operating on single line sections of track;
  • the medical fitness/assessment guidelines;
  • the medical conditions that can impair or incapacitate a train driver;
  • driver sign-on procedures;
  • sick leave policy;
  • emergency procedures; and
  • recommendations contained in the ATSB Footscray investigation report.

Copies of the report are available from the Director Public Transport Safety, Victorian Department of Infrastructure, Plaza Level, 80 Collins Street, Melbourne or by telephoning (03) 9655 6402.

Occurrence summary

Investigation number 2002/001
Occurrence date 18/06/2002
Location Epping
State New South Wales
Report release date 25/07/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Rail
Occurrence class Accident
Highest injury level Serious

Wharf contact by Sofrana Magellan

Summary

Investigation discontinued.

Occurrence summary

Investigation number 187
Occurrence date 01/11/2002
Location Brisbane
Report status Final
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Marine
Marine occurrence category Contact
Occurrence class Incident
Highest injury level None

Ship details

Name Sofrana Magellan
IMO number 8513443
Ship type Container
Flag A & B
Destination Brisbane

Lifeboat incident on board Hong Kong flag bulk carrier Ma Cho

Final report

Summary

On 8 December 2002, Ma Cho arrived in Devonport, Tasmania, to discharge a part cargo of fertiliser at number four berth on the western side of the river.

On 9 December, the master made the decision to conduct an abandon ship drill before the vessel was due to depart for Geelong. The drill commenced at about 1540 and the starboard lifeboat was prepared for lowering to the water.

At approximately 1548 the mate reported that the crew inside the lifeboat were seated and had fastened their safety belts. Lowering of the boat then commenced with one of the crew operating the davit winch brake from the deck. When the boat had been lowered approximately two metres from the davit head the after on-load release hook suddenly opened, releasing the after fall. The lifeboat's stern fell to leave the boat suspended vertically by the remaining forward fall with its stern swinging approximately five metres above the water. The boat crew were shaken by the incident but remained secured in their seats inside the now vertical lifeboat. The second mate had sustained a small cut over his left eye.

After the crew had disembarked, the lifeboat was lowered to the water to allow the on-load release system to be inspected. It was found that the cable operating the after hook was not properly secured by the saddle clamp under the operating unit. Each time the actuating handle was operated, lost motion was induced by the cable sliding through the clamp and this meant that the after hook was not resetting fully. The cable clamp was temporary repaired and then the lifeboat was housed in its davit. Ma Cho was subsequently cleared to complete the voyage to Geelong.

The report conclusions include:

  • The cable clamp securing the aft hook's operating cable adjacent to the operating mechanism had been modified which resulted in lost motion within the cable.
  • As a result of the lost motion in its operating cable, the after hook had not been fully reset when the previous lifeboat drill was conducted on 2 November 2002.
  • The design of the on-load release system was flawed with respect to the hook locking mechanism.
  • The ship's safety management system was deficient with respect to both the operating and maintenance instructions and to crew training on the on-load release system.

The report makes a general recommendation to ISM Code accreditation authorities regarding ship safety management systems as they relate to on-load release systems. The report also recommends that the lifeboat manufacturer and classification societies review the design of the on-load release system.

Occurrence summary

Investigation number 188
Occurrence date 09/12/2002
Location Devonport
State Tasmania
Report release date 30/06/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Lifeboat
Occurrence class Incident
Highest injury level Minor

Ship details

Name Ma Cho
IMO number 9118252
Ship type Bulk Carrier
Flag Hong Kong
Departure point Davenport, Tas

Equipment failure on board Australian registered bulk carrier Goliath

Final report

Executive summary

On 22 September 2002 the catastrophic failure of the main engine turbocharger disabled the cement carrier Goliath in Bass Strait. The replacement turbocharger failed in a similar manner on 12 February 2003, only four and a half months later, when Goliath was off Jervis Bay, again disabling the ship.

At 0107 on 22 September 2002, the Australian flag bulk cement carrier Goliath experienced a main engine turbocharger failure while the vessel was en route from Newcastle to Devonport when the turbocharger 'exploded' and disabled the ship's main engine.

At 1543 on 12 February 2003, while Goliath was en route from Devonport to Sydney, the turbocharger failed again. This time, the failure was witnessed by the second engineer who heard the rapid acceleration of the turbocharger before it exploded. Once again, the turbocharger had been damaged beyond repair and the ship was disabled.

The investigation report concludes that both turbocharger failures were similar and had occurred when the compressor discs burst due to overspeed. While it is not possible to state with certainty, the most likely mechanism leading to both overspeeds was a scavenge fire in the engine.

The ATSB delayed the release of these final investigation reports because of litigation involving the parties and because the investigations preceded and were not protected under the Transport Safety Investigation Act 2003.

Occurrence summary

Investigation number 186
Occurrence date 22/09/2002
Location Bass Strait
State Victoria
Report release date 21/06/2006
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Equipment
Occurrence class Incident
Highest injury level None

Ship details

Name Goliath
IMO number 9036430
Ship type Bulk carrier
Flag Australia
Departure point N/A
Destination N/A

Engine room fatality on Golden Bridge en route to Newcastle

Final report

On 10 December 2002, the third engineer aboard the bulk carrier Golden Bridge was killed whilst engaged in maintenance work in the engine room. A perspex sightglass exploded into his face when the fresh water generator he was working on was accidentally pressurised. The explosion blew the engineer backwards and he struck his head causing a fatal injury.

Occurrence summary

Investigation number 189
Occurrence date 10/12/2002
Location Off Norah Head
State New South Wales
Report release date 30/09/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Fatality
Occurrence class Serious Incident
Highest injury level Fatal

Ship details

Name Golden Bridge
IMO number 9118848
Ship type Bulk carrier
Flag Panama
Departure point Japan
Destination Port Kembla, NSW

Loss of the NSW registered fishing vessel Tamara

Final report

On 14 September 2002, two men were found drifting in a liferaft 30 miles east of Moreton Island, Queensland. The two men had been in the liferaft since their vessel, Tamara, had sunk some 14 days previously.

Occurrence summary

Investigation number 185
Occurrence date 01/09/2002
Location Off QLD Coast
Report release date 09/12/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Equipment
Occurrence class Serious Incident
Highest injury level None

Ship details

Name Tamara
Ship type Commercial fishing vessel
Flag Australia
Departure point Southport, Queensland
Destination Noumea

Fire in the hold of the general cargo vessel Marion Green

Final report

Summary

On 28 July 2002, the Netherlands flag general purpose cargo vessel Marion Green, of 11 894 gross tonnes, carrying 6000 tonnes of cocoa beans, was off the coast of Western Australia on passage from Fremantle to Adelaide.

At 1130 that morning a fire alarm was activated by the smoke detection system in No. 2 cargo hold. After a brief inspection through the open hold access by the mate and second mate, during which they saw some flames on top of the cargo, all openings were closed and the discharge of CO2 from the fixed firefighting installation was started. By 1715 that afternoon, 86 bottles of CO2 had been released into the hold.

At 0700 on the following day, a slight increase in hatch cover temperature was recorded. The master was advised by the vessel's managers to discharge the remaining 11 bottles of hold CO2 and to divert to Albany as a port of refuge.

Marion Green berthed in Albany at 1615 on 29 July. Additional bulk CO2 was delivered to the ship from Perth and this, too, was discharged into the hold over the next few days. On the morning of 31 July, the after panels of No. 2 hatch were opened for an inspection. Flames were seen on the top layers of cargo, and these were doused by the fire brigade after which the hatches were again closed, and more CO2 discharged into the hold. At 1400 the following day, 1 August, the hatch covers were once more opened and, after further flare-ups had been doused by the fire brigade, stevedores began discharging the cargo into sand bungs on the wharf. By 10 August all the cocoa bean cargo had been discharged and Marion Green sailed for Adelaide.

The report concludes that the investigation was unable to determine, exactly, the cause of the fire, but four distinct possibilities were examined. These were:

  • Self-heating of the cargo due to fungal growth
  • Ignition caused by the flammable characteristics of the phosphine used for fumigating the cargo
  • Cigarette ends discarded in the hold during loading of the cargo in Makassar
  • A cargo light that had been left in the hold on sailing from Makassar

It also concludes that:

  • the vessel's 'no smoking' policy was not properly enforced during cargo loading
  • insufficient CO2 was released into the hold in the early stages of the fire
  • inadequate information on the hazards of shipping cocoa beans was provided to the ship's staff and
  • the response to the fire, once the vessel was alongside, lacked co-ordination and a clear understanding of who had the responsibility and authority for dealing with it.

The report recommends that:

  • the shipowners enforce a strict 'no smoking' policy in the vicinity of cargo operations
  • the shipowners ensure that ship's masters are provided with all relevant information on the hazards of carrying organic cargoes and their fumigation
  • shippers, stevedores and ship's officers ensure that adequate ventilation channels are provided when stowing such cargoes and
  • deck watchkeeping officers log the isolation and stowage of all electrical equipment from the holds on completion of cargo operations.

Occurrence summary

Investigation number 183
Occurrence date 28/07/2002
Location Off WA Coast
State Western Australia
Report release date 09/12/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Fire
Occurrence class Incident
Highest injury level None

Ship details

Name Marion Green
IMO number 9164029
Ship type Multi-purpose general cargo
Flag Netherlands
Departure point Fremantle, WA
Destination Adelaide, SA

Grounding of the Korean flag bulk carrier Hanjin Dampier

Final report

Summary

At 1032 on 25 August 2002, the Korean flag bulk carrier Hanjin Dampier departed from the Hamersley Iron wharf at East Intercourse Island in the port of Dampier, Western Australia. A pilot was conducting the navigation of the ship which was loaded with iron ore and had a displacement of 233 158 tonnes with draughts of 17.94 m forward and 18.10 m aft.

At 1127, just after Hanjin Dampier passed number four Hamersley Channel beacons, two of the ship's three main generators stopped, leaving only one generator running and connected to the main switchboard.

At 1152, with the ship 1.3 miles east of Courtenay Head and making headway at a little over eight knots, the third generator's circuit breaker tripped open. With the total loss of power to the main switchboard the main engine stopped, and the ship lost steering. The rudder had stopped at 10 to starboard. As the ship slowed, it started to turn to starboard towards shallow water. The emergency generator failed to start automatically and, as a result, steering was not restored for some four minutes.

At 1202, Hanjin Dampier touched bottom. By about 1203 the ship had come to a stop on a heading of 047(T) in a position between the charted deep draught track and the Woodside Channel (20 29.7 degrees, 116 43.3 degrees).

Hanjin Dampier was refloated on the next spring tide, on 8 September, using five tugs and after 5000-6000 tonnes of cargo had been discharged. The ship had suffered only minor damage to the bottom shell plating and the ship was cleared by the classification society to continue trading until the next scheduled drydocking.

The report's conclusions include:

  • The ship grounded as a direct result of the loss of steering;
  • Steering was lost when the ship's three main generators tripped off the main switchboard due to water contamination of their fuel supply;
  • The emergency generator failed to start automatically due to a fault in one of its starting batteries;
  • The crew took no action nor instigated any contingency plan in the time leading up to the blackout when they could have reduced the risk to the ship; and
  • Lack of effective communication between the chief engineer and master contributed to the crew's failure to take any pre-emptive action.

The report makes three recommendations involving the testing of emergency power arrangements, bridge resource management training for engineers and the use of tugs in the port of Dampier.

Occurrence summary

Investigation number 184
Occurrence date 25/08/2002
Location Dampier
State Western Australia
Report release date 22/12/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Grounding
Occurrence class Incident
Highest injury level None

Ship details

Name Hanjin Dampier
IMO number 8811144
Ship type Bulk carrier
Flag Korea
Departure point Dampier, Western Australia
Destination Kwangyang, South Korea

Grounding of the container ship ANL Excellence

Final report

Summary

At 0318 on 19 July 2002, the Liberian flag container ship ANL Excellence embarked a pilot off Point Cartwright, Queensland, for the passage to Fisherman Islands container terminal in the Port of Brisbane. After arriving on the bridge, the pilot set up a portable electronic chart display equipped with a differential global positioning system, to allow him to independently monitor the passage to the berth.

The pilotage proceeded routinely. There were no other movements within the port or the approach channels during this time. The weather was reasonable, though visibility was reduced at times by passing rain showers.

At 0518, ANL Excellence passed beacon E1 and entered the East Channel. Rain was falling at this time and the bridge window wipers were operating. Ahead, the starboard lateral beacon E3 and the port lateral beacons E2 and E4 could be seen. A temporary, starboard lateral buoy was marking the position of the cardinal beacon E5 which had been destroyed by a ship some 15 months previously. This temporary buoy was not seen by anyone on the bridge.

As the vessel passed starboard lateral beacon E3, the pilot ordered starboard rudder to bring the ship to a heading of 240 and then called Brisbane Port Control to advise that the ship would be at the entrance channel at 0600.

The master, sitting in front of one of the two radars, realised that the relative bearings of beacons E4 and E2 were changing and went to the helmsman to see what was happening. The pilot went to his electronic chart system, which had reverted to a blank screen stand-by mode. He tapped a key and when the chart was restored, he suddenly realised that he had ordered the course alteration too soon.

The main engine was stopped and put astern, but ANL Excellence grounded before the ship had begun to slow.

The ship was refloated on the high tide of the afternoon of 19 July 2002, using its main engine and with the aid of tugs. Following an inspection of the hull, both internally and externally on 20 July, the vessel was cleared by the Australian Maritime Safety Authority, and its classification society to continue in service.

The report conclusions include:

  • The pilot did not follow his normal procedure of checking the position of the course alteration using his portable electronic chart system.
  • The temporary buoy marking the original position of the original east cardinal beacon E5 (the turning mark) was obscured by rain.
  • The green light on the temporary buoy was not as conspicuous as a white light, which would normally be associated with a cardinal navigation mark.
  • Although not suffering from chronic fatigue, the pilot's performance was probably affected by the trough in his circadian rhythm associated with the hours between 0400 and 0600.
  • The pilot's electronic chart system was placed at a significant distance from where he was standing, with its display in power saving mode at a critical moment.
  • The bridge team did not detect the erroneous helm order and failed to challenge the pilot.

The report recommends that:

  • Where port authorities use a buoy or other temporary aid to replace an established navigation aid, the shape and the light characteristics of the temporary aid should be consistent with those of the aid it replaces.
  • Brisbane Marine Pilots should review the power management settings and placement of a pilot's portable electronic chart system to ensure that the information displayed remains easily visible from the pilot's conning position at all times during a pilotage.

Conclusions

These conclusions identify the different factors contributing to the incident and should not be read as apportioning blame or liability to any particular individual or organisation.

Based on the evidence available, ANL Excellence grounded on Middle Banks on 19 July 2002 as a result of the pilot erroneously ordering an alteration of course at the starboard lateral beacon E3 instead of at the temporary starboard lateral buoy marking the position of the original east cardinal beacon E5. The following are considered to be factors in the incident:

  1. The pilot did not follow his normal procedure of checking the position of the course alteration using his portable electronic chart system.
  2. The temporary buoy marking the original position of the original east cardinal beacon E5 (the turning mark) was obscured by rain.
  3. The green light on the temporary buoy was not as conspicuous as a white light, which would normally be associated with a cardinal navigation mark.
  4. Although not suffering from chronic fatigue, the pilot's performance was probably affected by the trough in his circadian rhythm associated with the hours between 0400 and 0600.
  5. The pilot's electronic chart system was placed at a significant distance from where he was standing, with its display in power saving mode at a critical moment.
  6. The bridge team did not detect the erroneous helm order as a result of:
    1. Both the master and mate were probably fatigued as a result of their hours of work during the passage through the Great Barrier Reef, which was exacerbated by the 'time of day' effect.
    2. Neither the master nor the mate were sufficiently aware of the ship's situation, at the time, to challenge the pilot's premature order for the course alteration.
    3. Insufficient attention was paid to the ship's radar display.
    4. The navigation chart in use by the ship did not show the temporary replacement of E5 cardinal beacon with a temporary starboard lateral buoy marking the southeast extremity of Middle Bank.
    5. The interpersonal tension between the master and mate effectively nullified the active participation of one qualified navigator in the bridge team.

Occurrence summary

Investigation number 181
Occurrence date 19/07/2002
Location Moreton Bay
State Queensland
Report release date 19/05/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Grounding
Occurrence class Incident
Highest injury level None

Ship details

Name ANL Excellence
IMO number 9134517
Ship type Cellular container ship
Flag Liberia
Departure point Port of Brisbane, Qld

Fatality while sailing from Dampier Taharoa Express

Final report

Taharoa Express

Taharoa Express is a Panama flag bulk carrier of 145 842 tonnes deadweight at a summer draught of 17.42 m. The vessel, owned by Pacific Transport Trading SA and managed by Hachiuma Steamship Company, was on charter to NYK Line, Tokyo.

Classed with Nippon Kaiji Kyokai, the vessel was built in 1990 by Hyundai Heavy Industries in South Korea. It is of standard bulk carrier design with 9 cargo holds located forward of the accommodation superstructure. It has an overall length of 269 m, a moulded breadth of 43 m and a moulded depth of 23.8 m. Propulsive power is provided by a 5-cylinder B&W 5S70MC diesel engine of 11 974 kW driving a single fixed pitch propeller which gives the ship a service speed of 14 knots.

At the time of the incident, Taharoa Express had a complement of 25. The master, mate and the chief engineer were Japanese and the other officers and crew were Filipinos. The master and other officers all held appropriate qualifications.

Conclusions

The following factors are considered to have contributed to the incident:

  • The seaman was standing almost directly over the fairlead roller for the mooring rope and was not warned that he should have been in a safer position;
  • It is likely that the bosun, thinking that the breastlines had been released, operated the winch to recover the lines, resulting in tightening of the line that was still attached to the mooring hook.

In addition, although tests on the hook were not conclusive, one or more of the following possibly occurred:

  • The initial attempt to release the hook partially altered the position of the release system resulting in a release of the hook under tension;
  • Dirt or rust had prevented the mooring hook from being correctly reset;
  • The mooring hook was not correctly reset.

It is possible that modifications to the remote release mechanism might also have been a factor in the hook releasing.

Occurrence summary

Investigation number 180
Occurrence date 11/07/2002
Location Dampier
State Western Australia
Report release date 26/08/2003
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Marine
Marine occurrence category Fatality
Occurrence class Serious Incident
Highest injury level Fatal

Ship details

Name Taharoa Express
IMO number 8903117
Ship type Bulk carrier
Flag Panama