On 20 February 2013, the pilot of a Cessna 310 aircraft, registered VH‑TWN (TWN), arrived at Wagga Wagga Airport to conduct a freight charter flight to Albury and Corowa, New South Wales.
In preparation for the flight, the pilot reviewed the applicable weather forecasts and Notice to Airmen (NOTAM) on a computer. At that time, another company employee initiated a conversation with the pilot. The pilot completed his pre-flight preparations and the aircraft departed at 0730 for Albury.
Prior to 0800, four workers at the Corowa aerodrome commenced laying unserviceability cross markers on runway 05/23. The runway had been declared closed from 0800 to 1800 due to works in progress (WIP); runway 14/32 remained open.
At about 0810, TWN departed Albury for Corowa. When 19 NM and 10 NM from Corowa, the pilot reported broadcasting an inbound call on the common traffic advisory frequency (CTAF). The pilot broadcast additional calls on the CTAF advising he was on base and final for runway 23.
The workers at Corowa were in the process of placing the last unserviceability cross marker near the runway 05 threshold, when they observed TWN on final approach for runway 23. The workers vehicle was also positioned on the runway. The workers and vehicle vacated the runway.
At about 0825, TWN landed on runway 23. Immediately after landing, when about 90-120 m along the runway, the pilot observed an unserviceability cross marker on the ground.
The workers were monitoring the CTAF on a hand held radio, but no broadcasts from TWN were reportedly heard.
This incident demonstrates the importance of maintaining a high level of vigilance, even when conducting familiar tasks; and the unexpected nature of distractions and the impact they can have on pre-flight preparations.
At about 1207 on 21 March 2013, a Robinson Helicopter Company R44 helicopter (R44), registered VH-HWQ, landed at a grassed area adjacent to a function centre at Bulli Tops, New South Wales. Shortly after landing, the helicopter was observed to simultaneously lift off, yaw right through 180° and drift towards nearby trees. The helicopter struck branches of the trees before descending, impacting the ground nose low and rolling onto its right side. A short time after coming to rest a fire started and engulfed the helicopter. The pilot and three passengers were fatally injured.
What the ATSB found
The circumstances of this accident were consistent with the helicopter lifting off following a deliberate or inadvertent collective input. The helicopter’s main rotor blades subsequently contacted nearby trees resulting in a loss of control and impact with the ground. The impact sequence resulted in a substantial fuel leak that was followed by an intense fire. This accident was similar to two other relatively recent fatal accidents in Australia involving R44s fitted with all-aluminium fuel tanks in which there was a fatal post-impact fire (PIF) following an otherwise survivable impact. Statistical analysis of helicopter accidents that occurred in Australia and the United States (US) between 1993 and 2013 identified a significantly higher proportion of PIF involving R44s than for other similar helicopter types. That analysis also identified that, despite the introduction of requirements for newly certificated helicopters to have an improved crash-resistant fuel system (CRFS) some 20 years previously, several helicopter types were still being manufactured without a CRFS and that many of the existing civil helicopter fleet were similarly not fitted with a CRFS.
What's been done as a result
Following this accident the Civil Aviation Safety Authority (CASA) took action to increase compliance with the helicopter manufacturer’s Service Bulletin 78B (SB-78B), requiring the fitment of bladder-type fuel tanks and other fuel system improvements. While recognising the action taken by CASA, due to concern that a significant number of Australian owners and operators had at that stage not taken steps to comply with the service bulletin, and were very unlikely to be able to do so by the required date of 30 April 2013, the ATSB released safety recommendation AO-2013-055-SR-001 to CASA that further action be taken. In response CASA released airworthiness directive AD/R44/23 requiring all owners of R44 helicopters in Australia to comply with SB-78B by the required date. Several other national airworthiness authorities (the South African Civil Aviation Authority, the Civil Aviation Authority of New Zealand and the European Aviation Safety Agency) subsequently mandated compliance with SB-78B. At the time of publishing this report the State of Design and Manufacture of the R44 helicopter had not mandated compliance with SB-78B.
The ATSB has issued a safety recommendation to the US Federal Aviation Administration (FAA) that they take action to ensure all R44 operators and owners comply with the manufacturer's Service Bulletin SB-78B and fit bladder-type tanks to improve resistance to post-impact fuel leaks. In addition, the ATSB also recommend that the FAA and European Aviation Safety Agency take action to increase the number of existing and newly-manufactured helicopters that are fitted with a crash-resistant fuel system.
Safety message
This accident highlights the catastrophic consequences of fuel-fed post-impact fire and that the most effective defence is to prevent the fire from occurring at impact by containing the fuel on board, preventing ignition, or both. In that context, the ATSB strongly encourages the fitment of a crash-resistant fuel system where possible.
Preliminary report
Report release date: 05/04/2014
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
Safety summary
What happened
At about 1207 local time on 21 March 2013, a Robinson Helicopter Company R44 helicopter (R44), registered VH-HWQ, was manoeuvring at a grassed area at Bulli Tops, New South Wales. Shortly after landing, the helicopter lifted off and turned to the right. The main rotor struck branches of a nearby tree, and the helicopter descended and then rolled over onto its right side. A fire started on the grass under the rotor mast and the cabin. The pilot and the three passengers were fatally injured.
What the ATSB found
The circumstances of this accident are consistent with two recent R44 accidents in Australia involving low-energy impacts that resulted in the all-aluminium fuel tanks being breached and a fuel-fed fire. R44 accidents result in a significantly higher proportion of post-impact fires than for other similar helicopter types. The accident helicopter was equipped with an all-aluminium tank.
On 20 December 2010 the Robinson Helicopter Company issued Service Bulletin SB-78 providing for the replacement of all-aluminium tanks in R44 helicopters with bladder-type tanks that substantially reduce the likelihood of post-crash fires. On 28 September 2012 the Robinson Helicopter Company revised and reissued the service bulletin as SB-78B. This revision brought forward the compliance date for the service bulletin to 30 April 2013. The ATSB has assessed that about 100 Australian R44 helicopters will not have met the service bulletin by the due date.
What's been done as a result
In response to this accident, the Civil Aviation Safety Authority (CASA) has confirmed its understanding that the great majority of Australian R44 helicopter owners are legally required to comply with Service Bulletin SB-78B. CASA has also undertaken to contact owners who may not be required to comply and then consider further action depending on the response to that contact.
The ATSB remains concerned at the significant risk that many R44 helicopters will not comply with the service bulletin and has recommended that CASA take further action to ensure compliance.
Safety message
The fitment of bladder-type fuel tanks to R44 helicopters is a very important safety enhancement that could save lives and is very strongly encouraged. In addition, regulators and investigation agencies in other countries should take note of this report and consider what steps they can take to increase compliance with the manufacturer’s safety bulletin.
On 19 March 2013 at about 1016 Eastern Daylight-saving Time, the pilot of a Cessna 172S aircraft, registered VH‑EUH (EUH), made a 10 NM inbound broadcast on the Point Cook CTAF advising that he intended to track overhead Point Cook for Avalon at 2,500 ft. The pilot was also monitoring the Melbourne Centre frequency
At about the same time, a Piper PA‑44‑180 aircraft, registered VH‑TYS (TYS), became airborne at Point Cook, for an IFR training flight. The pilot under training was flying under the hood and the instructing pilot was making all radio calls to Melbourne Centre and broadcasts on the CTAF. The flight crew of TYS did not hear the 10 NM CTAF broadcast made by EUH.
As TYS tracked southbound about 3 NM east of Point Cook and passing about 2,000 ft on climb to 3,000 ft, the instructing pilot deselected the CTAF. The pilot flying then turned right to track in a northerly direction, in anticipation of an airways clearance to enter Melbourne controlled airspace.
At about the same time, as EUH passed abeam Point Cook to the north-west, the pilot broadcast that he was leaving 2,500 ft for 4,500 ft.
At 1022, as TYS was levelling off at 3,000 ft about 1 NM west of Point Cook and in uncontrolled airspace, the instructing pilot looked to the right and observed a C172 in their 2 o’clock position about 100 m away at the same level. He called ‘taking over’ and immediately pushed the control column forward to descend below the traffic. The C172 flew about 50 to 100 ft above and about 9 to 12 m behind TYS. The instructing pilot then climbed the aircraft to 3,000 ft and the flight continued with no further incident.
The pilot of EUH reported that he did not see TYS.
A pilot of another aircraft operating in the Point Cook circuit at the time reported hearing a broadcast by EUH on the CTAF.
The ATSB often receives reports from pilots that another aircraft is flying too close to them in uncontrolled airspace. Three quarters of these reports involve pilots flying within 10 NM of a non-towered aerodrome. As a result, the ATSB has highlighted safety around non-towered aerodromes as one of its SafetyWatch priorities.
The ATSB publication A pilot’s guide to staying safe in the vicinity of non-towered aerodromes, AR‑2008‑044(1), noted that over 200 occurrences between 2003 and 2008 were found where pilots flying within 10 NM of a non-towered aerodrome may not have been broadcasting or maintaining a continuous listening watch on the CTAF.
Broadcasting on and monitoring the CTAF are key ways for pilots to establish traffic awareness, in the vicinity of non-towered aerodromes. The ATSB’s Limitations of the See-and-Avoid Principle study has shown that the effectiveness of a search for other traffic is eight times greater under alerted see-and-avoid circumstances, when a radio is used effectively in combination with a visual lookout, than when just un-alerted, when no radio is used.
On the evening of the incident there were six aircraft in the circuit, including two Cessna 172 aircraft (C172). Both aircraft were engaged in flying training, one a dual flight (dual C172) and the other solo (solo C172).
The pilot of the solo C172 was instructed to follow the preceding aircraft, the dual C172. As the solo C172 approached the position where the pilot normally turned from downwind onto base, the pilot looked to the left and identified what he thought were the flashing lights of the aircraft he had been instructed to follow. The turn brought the solo C172 onto a base leg inside that of the dual C172.
Approaching the position where he was to turn onto final, the pilot of the solo C172 again misidentified the aircraft he had been instructed to follow. As the pilot of the solo C172 levelled out on final, ATC queried whether he still had the aircraft he had been instructed to follow in sight. Before he could answer, the instructor pilot of the dual C172 transmitted he was descending. After acknowledging the dual C172, ATC instructed the pilot of the solo C172 to go-around.
As a result of this occurrence, the operator of the solo C172 has advised the ATSB that they have implemented a night-flying checklist to record details briefed to students on expected flight conditions and traffic densities. Also, as a result of this occurrence, the operator of the dual C172 has implemented a procedure to liaise with other training organisations at Moorabbin to determine the number of aircraft programmed for night circuits.
A review conducted by the ATSB found that most of the midair collisions in Australia had occurred in the circuit area, and a high proportion of those on the final approach or the base-to-final turn. Though the review noted that there was a wide variety of contributing factors in the collisions with no dominant factors, the circumstances of a majority of the collisions were consistent with the inherent difficulties in sighting aircraft in time to avoid a collision.
On 19 March 2013, EL Zorro freight train 9261 travelling to Warrnambool, Victoria collided with a northbound motor vehicle at the Brown Street level crossing in Allansford (21 km east of Warrnambool) at about 0730. Vehicular traffic across the Brown Street level crossing was controlled by warning and stop signs (passive controls).
The motor vehicle driver sustained fatal injuries. The train crew were not injured in the accident. The motor vehicle was severely damaged while the train sustained minor damage.
What the ATSB found
The ATSB found that the driver of the motor vehicle did not come to a stop at the railway crossing Stop line and proceeded into the level crossing and the path of the freight train. The ATSB concluded that the driver’s familiarity with this crossing, combined with the expectation that a train would not be present due to the low frequency of rail traffic on this line, probably influenced the motorist’s behaviour.
When at the Stop line south of the crossing – the direction the motor vehicle driver approached the crossing – there was adequate sighting to the east, the direction from which the train approached.
For approaches other than the occurrence scenario, the level crossing did not meet the requirements of Australian Standard AS 1742.7-2007, Manual of uniform traffic control devices, Part 7: Railway crossings. This issue was not found to be contributory to this accident.
Prior to this accident, this level crossing was identified as having sighting issues by the infrastructure manager V/Line and was included in the 2013/14 Fix Country Level Crossings Program, a Victorian Government funded program to upgrade rural level crossings by equipping them with active controls including lights, bells and boom barriers.
What's been done as a result
Warrnambool City Council has temporarily closed the Brown Street Level Crossing until it is equipped with active traffic controls.
A minor deficiency with respect to the signage north of the level crossing on Brown Street has been rectified by the Warrnambool City Council.
Safety message
This occurrence highlights the need for motor vehicle drivers using railway level crossings to be vigilant, observe road warning signs, obey road rules and look out for trains.
On 20 March 2013, an engineer on board the bulk carrier Nireas was carrying out the routine task of draining water from the ship’s main air receiver when the air receiver drainage pot observation window exploded. The engineer was fatally injured by flying debris from the observation window.
What the ATSB found
The ATSB investigation found that the drainage pot observation window glass exploded when it was exposed to the air receiver pressure. This pressure accumulated in the drainage pot because the water being drained restricted the flow into and through the pot outlet line.
The investigation also found that the shipyard which built the ship, and designed and installed the condensate drain system, considered that the drain system was open to atmosphere. When the design of the drainage pot was modified to create a closed system, the shipyard did not ensure that the design was adequately engineered, tested and approved prior to installation, despite having procedures in place which should have ensured such scrutiny.
During the course of the investigation, it was brought to the attention of the ATSB that similar designs of drainage systems had been, and continued to be, fitted in ships by various shipyards around the world.
What's been done as a result
All similar drainage pot observation window glasses were removed on board Nireas and its sister ship. The drainage pots were later modified, under the supervision of Lloyd’s Register, to include a partly open steel plate in place of the observation glass.
The ship builder advised the ATSB that it had contacted all owners of ships in which it had fitted this design of drain system. They informed them of the accident and requested that all observation glasses be removed and for the pots to remain unobstructed.
In July 2013, the Australian Maritime Safety Authority (AMSA) issued Marine Notice 11/2013, to draw industry attention to this accident and request that appropriate safety action is taken where such systems are encountered on board ships. This Marine Notice is being updated and the latest version is available on the AMSA website: www.amsa.gov.au
The ATSB has also issued a safety advisory notice addressed to all classification societies, advising them of the accident, the safety implications of the installation and use of closed condensate drainage/inspection systems and of the need to draw the attention of the shipping industry to these issues.
Safety message
This accident identifies the need to follow a formal process of risk assessment when considering possible equipment modifications. Such a process should ensure that all associated risks are identified, considered and appropriately treated.
Preliminary report
Report release date: 31/05/2013
Safety summary
The information contained in this preliminary report is derived from the initial investigation of the occurrence. Readers are cautioned that it is possible that new evidence may become available that alters the circumstances as depicted in the report.
What happened
On 20 March 2013, an engineer on board the bulk carrier Nireas was fatally injured after being struck by flying debris when the observation window of a main air receiver drainage pot exploded. At the time of the explosion, the ship was at anchor off Gladstone, Queensland, and the engineer was carrying out the routine task of draining water from the pressurised air receiver.
What the ATSB found so far
Initial analysis of the accident indicates that the observation window glass of the drainage pot exploded when it was exposed to the air receiver pressure. However, all of the factors which contributed to the failure of the glass have not yet been established.
What's been done as a result
All six similar drainage pot observation window glasses on board Nireas have been removed pending verification of the drainage arrangement design to the satisfaction of Lloyd’s Register, the ship’s classification society.
The ATSB has contacted Nireas’ managers, the ship builder, Lloyd’s Register, the flag state (Liberia) and the Australian Maritime Safety Authority. They were all informed of the accident and asked that the owners and operators of any ships fitted with similar systems be advised of this accident and that appropriate safety action should be taken by them to prevent similar accidents on board their ships.
Nireas’ managers have advised the ATSB that they have also removed the drainage pot observation window glasses from the only other ship managed by them that is fitted with similar drainage arrangements.
The ship builder has advised the ATSB that it has contacted all owners of ships in which it had fitted this design of drain system informing them of the accident and requesting that all observation glasses be removed and for the pots to remain unobstructed.
Investigation direction
The investigation is ongoing and it will focus on determining why the observation glass failed, whether the drainage pot was fit for purpose and whether there were any underlying issues in relation to the design, construction, testing, or certification of the drainage pot.
On 17 March 2013, the owner-pilot of an amateur-built scale-replica Spitfire aircraft (VH-VSF) was participating in an air display at Parafield Airport, South Australia. The pilot performed a number of airborne passes above the runways in various directions and completed the display with a slow speed pass at 400 ft with the landing gear and some wing flap extended.
Towards the end of this pass the pilot radioed the tower to coordinate a landing and accepted runway 21 Left with an 11 kt crosswind. By now the pilot had turned right and the Spitfire was near the extended runway centreline and 1 km from the runway threshold at a slow speed. A left turn was then observed and, soon after, a wing dropped and the aircraft entered a steep descent. The aircraft crashed in a factory car park, fatally injuring the pilot and substantially damaging the aircraft.
What the ATSB found
The ATSB found that while coordinating a landing clearance with air traffic control and flying a low-level circuit with a close downwind and base in turbulent conditions, the pilot inadvertently allowed the airspeed to decay. In the subsequent turn (downwind) to adjust the circuit the aircraft aerodynamically stalled, descended steeply, and impacted the ground. The aircraft was prone to aerodynamically stall with little or no aerodynamic precursors and it was not fitted with a stall warning device, increasing the risk of inadvertent stall.
Safety message
Flying in an air display is different to normal operations and places additional demands on a pilot. Pilots who participate in air displays should consider the demands involved and to the extent possible ensure that the complete sequence, including landing, is planned and rehearsed.
Although amateur-built aircraft operated in the experimental category are not required to be fitted with a stall warning device (preferably with aural output), owner-pilots should consider the benefits of such devices as a last line of defence against stalling.
Update
Report release date: 23/07/2013
Updated: 23 July 2013
At about 1350 Central Daylight-saving Time[1] on 17 March 2013, an amateur built, 80 per cent scale replica of the Supermarine Spitfire Mk XXVI, registered VH‑VSF (VSF), took off from runway 21R at Parafield Airport, South Australia. The pilot was participating in an air display held in support of a local aircraft museum. Over the following 7 minutes the pilot completed a handling display orientated along runway 21/03 that was described by witnesses as relatively sedate, with a few steep turns with bank angles up to 60°, but no aerobatics. The weather was clear with a gusty south-easterly wind of up to 20 kt (37 km/h).
At the completion of his routine the pilot completed a final pass of the crowd on a close right downwind leg for runway 21 at about 350 ft above ground level. The aircraft, which had been operated in the clean configuration and at speeds around 120‑150 kt, was slowed to about 80 kt and configured with the landing gear down and a stage of landing flap as it passed the spectators (Figure 1).
Figure 1: Photograph taken of the Spitfire shortly before the accident as it flew past the spectator area on a downwind position for runway 21 at about 350 ft
Source: Airshow spectator, reproduced with permission
On the downwind leg the pilot communicated his intention to land to the air traffic control tower and enquired whether the wind still favoured a landing on runway 21. The aerodrome controller informed the pilot that the crosswind component was 11 kt (20 km/h) on runway 21 and runway 08 and cleared the pilot to manoeuvre as required to final runway 21L.[2]
A significant number of witnesses, some with piloting experience, observed the aircraft turn right base for runway 21L. They recalled that the aircraft appeared to be flying very slowly prior to an abrupt left turn away from the runway. Their accounts described a loss of control that was consistent with an aerodynamic stall followed by a significant wing drop. The aircraft was then observed to descend steeply toward the ground with a degree of spiral evident along the descent path before being lost to sight behind trees and buildings.
The aerodrome controller witnessed the aircraft descending out of sight and immediately instigated the aerodrome emergency response. A short time later the wreckage of the aircraft was located by emergency services in a factory car park about 1.5 km north of the runway 21L threshold. The pilot sustained fatal injuries and the aircraft was substantially damaged by impact forces (Figure 2). There was no fire.
Figure 2: Aircraft wreckage
Source: ATSB
Damage to the aircraft was consistent with it descending steeply into terrain at a high rate of descent in a wings-level, nose-down attitude. There was no evidence of in-flight structural failure. All of the aircraft’s components were accounted for at the accident site, with no evidence of pre-impact damage. Continuity of the aircraft’s flight and engine control systems was established and on-site evidence indicated that the engine was producing power at ground impact. The fuel tank ruptured on impact with the result that no fuel was available for testing. Examination of the airframe found that the aircraft did not incorporate any stall warning system.
A number of components were recovered from the accident site for technical examination including a global positioning system (GPS) receiver. The wreckage was documented and transported to a secure location for further examination as required.
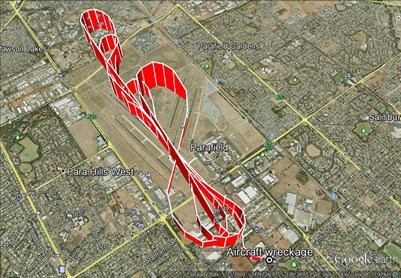
Australian Transport Safety Bureau technical specialists examined the GPS receiver. That examination found that track data was retained in the receiver’s non-volatile memory. The GPS data for the accident flight was downloaded and is depicted at Figure 3.
Figure 3: Accident flight data recovered from GPS receiver[3]
Source: Google earth
A review of the recorded GPS data indicated that the aircraft descended to about 350 ft above ground level and the groundspeed reduced to about 80 kt on the downwind leg. As the aircraft turned onto the base leg for runway 21L, a gradual increase in height to 485 ft and reduction in groundspeed to 55 kt was evident. The position of the aircraft in relation to the runway at this point indicates that a tight turn would most likely have been required to line up on the runway centreline. It is possible that the pilot made a deliberate left turn away from the runway at this stage to allow more room to manoeuvre for final.
The GPS-recorded path of the aircraft was consistent with witness observations and, in combination with recorded wind data from the automatic weather station at Parafield Airport, indicates that the aircraft’s airspeed was close to the stall speed on base leg and most likely below stall speed as it abruptly turned left away from the runway. The GPS recorded time interval from the commencement of the base turn until the collision with terrain was about 20 seconds.
The reduced scale replica Spitfire Mk XXVI is a conventionally-configured, low-wing cantilever monoplane that is manufactured in kit form for construction by owner‑builders. The pilot constructed VSF in 2006 and had maintained it in accordance with the Civil Aviation Regulations since that time.
The pilot held a Commercial Pilot (Aeroplane) Licence and his pilot’s logbook indicated he had 1,665 hours flight experience, 190 of which were on the kit-built Spitfire. The pilot was the sole pilot of the aircraft, held a Class 2 Medical Certificate and was reported to have been rested and in good health prior to the flight. He was described as being meticulous with his approach to flying and maintaining the aircraft.
The investigation is continuing and will include:
further examination of recovered components
analysis of aircraft performance during the flight
review of operational factors and the recorded data.
The final investigation report is planned for release to the public during October 2013.
The information contained in this web update is released in accordance with section 25 of the Transport Safety Investigation Act 2003 and is derived from the initial investigation of the occurrence. Readers are cautioned that new evidence will become available as the investigation progresses that will enhance the ATSB's understanding of the accident as outlined in this web update. As such, no analysis or findings are included in this update.
[1] Central Daylight-saving Time (CDT) was Coordinated universal Time (UTC) + 10.5 hours.
[2] The available runways at Parafield are oriented east-to-west (runways 08/26) and north-north-east-to-south-south-west (runways 03/21). Runways left and right are available in each direction.
[3] The data is represented by a series of individual GPS-recorded track points that have been joined together using a series of straight lines.
On 15 March 2013, a student pilot was conducting solo circuit training at Jandakot Airport, Western Australia, in a Grob G‑115C, registered VH-ZTM (ZTM).
At 1135 Western Standard Time, on the student’s third solo circuit to runway 06R, ZTM began to drift to the left of the runway centreline. The student elected to go-around and applied full power. Following the application of power, the nose pitched up abruptly and the aircraft then rolled to the left before pitching nose down. The left-wing tip contacted the ground, and the nose gear and right main gear collapsed before the aircraft came to a stop. The student pilot was able to exit the aircraft without injury, however the aircraft sustained substantial damage.
As a result of this occurrence, the flight training school has advised the ATSB that they are taking the following safety actions:
Increased emphasis on Stabilised Approach Criteria to be made during pre-flight briefings.
Instructor training and standardisation to include more emphasis on the essential use of rudder.
Inclusion on the training syllabus of an upper air exercise prior to first solo, to check student use of rudder and go-around procedures.
A more detailed brief on landing technique, for the G115C, to be included in the standard operating procedures.
A go-around is an aborted landing of an aircraft that is on final approach. The Aircraft Owners and Pilots Association (AOPA) has identified that for the ten-year period, between 1994 and 2003, accidents that occurred during a go-around accounted for approximately 6 % of the total accident rate for general aviation. During a go-around the aircraft is trimmed for landing, not for going around and the pilot will need to be positive with attitude changes as power is applied.
On the evening of 25 February 2013, a Boeing 737-838 aircraft, registered VH-VYE and operated by Qantas Airways Limited, was conducting a scheduled passenger service from Canberra Airport, Australian Capital Territory to Brisbane Airport, Queensland.
At 2110 Eastern Daylight-saving Time, about 115 NM (213 km) from Brisbane, and as the aircraft approached the descent point for Brisbane Airport, the aircraft’s autopilot unexpectedly commenced climbing the aircraft. The crew disconnected the autopilot and descended the aircraft.
During the descent to an air traffic control-cleared level the aircraft rolled left and deviated laterally from the flight plan track. The autopilot was subsequently re-engaged and the aircraft was manoeuvred to re-intercept the flight-planned track. The remainder of the flight was uneventful and the aircraft landed on runway 01 at Brisbane Airport.
What the ATSB found
The ATSB found that the auto-flight system allowed the capture of the Brisbane Airport runway 01 instrument landing system (ILS) glideslope and the aircraft unexpectedly climbed to intercept the signal, which had itself been affected by atmospheric refraction. The preconditions for the occurrence were that the Canberra and Brisbane ILS frequencies were the same, this frequency remained active in the aircraft’s navigation system and, shortly after reaching top of climb out of Canberra, the auto-flight system’s approach mode was inadvertently armed. This meant that when the aircraft was within range of the Brisbane ILS signal, the glideslope would become the active vertical flight mode. The configuration of the auto‑flight system logic on the operator’s Boeing 737 fleet allowed the aircraft to capture and follow a glideslope signal despite not being on the localiser.
The ATSB also found that contrary to the flight crew’s intent, after dis-engaging the autopilot, it was not re-engaged, resulting in a lateral deviation from the planned flight path.
Safety message
This occurrence highlights the human performance limitations with respect to monitoring and detecting mode reversions and flight mode annunciator (FMA) changes in automated aircraft. Flight crew are reminded of the importance of regularly identifying and confirming the flight modes displayed on the FMA.
On 8 March 2013, the flight crew of a Qantas Airways Limited (Qantas) A330 aircraft, registered VH-EBV, was conducting a visual approach to Melbourne Airport, Victoria. The captain was the pilot flying with autopilot engaged.
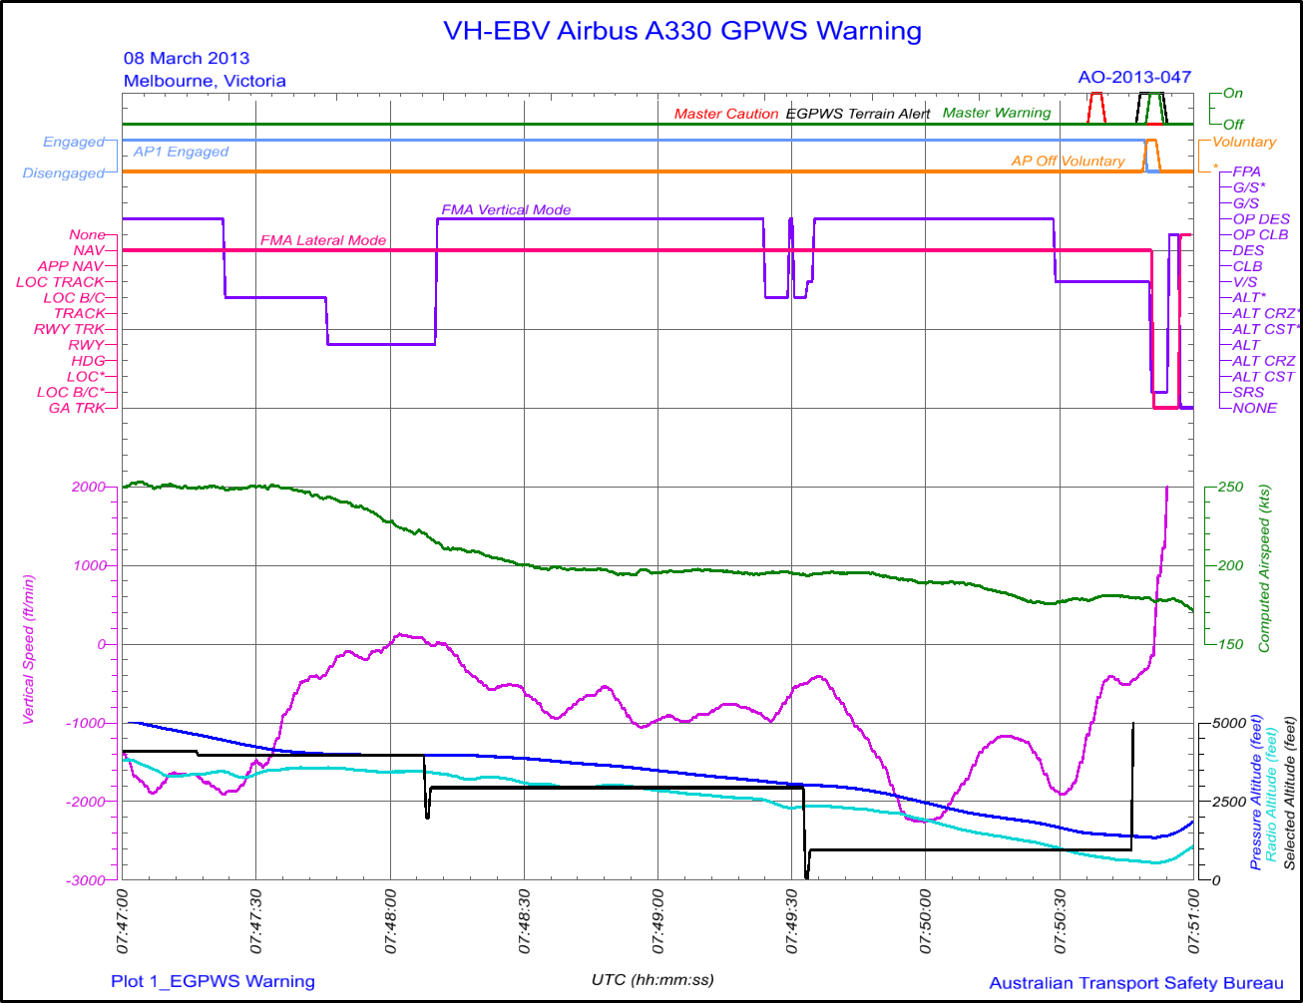
Soon after being cleared for the approach, on descent through 3,000 ft, the captain set an altitude target of 1,000 ft in the autoflight system and selected the landing gear down, the first stage of wing flap and 180 kt as the target speed. The descent was continued in autoflight open descent mode and reached a maximum of 2,200 ft/min. As the aircraft was descending through about 1,800 ft the first officer advised the captain that they were low. The captain reduced the rate of descent by selecting autoflight vertical speed mode but a short time later the enhanced ground proximity warning system (EGPWS) provided ‘TERRAIN’ alerts followed by ‘PULL UP’ warnings. The crew carried out an EGPWS recovery manoeuvre and subsequently landed via an instrument approach.
At the time of the EGPWS alert the aircraft had descended to 1,400 ft, which in that area was 600 ft above ground level, with 9 NM (17 km) to run to touchdown. This was 100 ft below the control area lower limit and 1,900 ft below a normal 3° descent profile.
What the ATSB found
The ATSB found that during the visual approach the captain’s performance capability was probably reduced due to the combined effects of disrupted and restricted sleep, a limited recent food intake and a cold/virus. The captain assessed the aircraft’s flight path using glide slope indications that were not valid. This resulted in an incorrect assessment that the aircraft was above the nominal descent profile.
In addition, the combination of the selection of an ineffective altitude target while using the autoflight open descent mode and ineffective monitoring of the aircraft’s flight path resulted in a significant deviation below the nominal descent profile. The flight crew’s action in reducing the aircraft's rate of descent following their comprehension of the altitude deviation did not prevent the aircraft descending outside controlled airspace and the activation of the EGPWS.
The ATSB also identified that limited guidance was provided by Qantas on the conduct of a visual approach and the associated briefing required to ensure flight crew had a shared understanding of the intended approach.
What's been done as a result
In response to this occurrence Qantas updated their training material for visual approaches and enhanced similar material in their captain/first officer conversion/promotion training books. In addition, targeted questions were developed that required check pilot signoff for proficiency. Finally, visual approaches were included as a discussion subject during flight crew route checks for the period 2013–2015.
Safety message
The ATSB reminds operators and flight crew of the importance of continuous attention to the appropriateness of the autoflight system modes in use. Equally, the ATSB stresses the importance of continually monitoring descent profiles, irrespective of the type of approach being flown and the level of automation being used. For flight crew, this occurrence illustrates the need to communicate their intentions and actions to ensure a shared understanding of the intended approach.
The occurrence
On 8 March 2013, a Qantas Airways Limited (Qantas) flight crew was rostered to operate an Airbus A330 aircraft, registered VH-EBV, on a scheduled passenger flight from Perth, Western Australia to Sydney, New South Wales, and then to Melbourne, Victoria followed by a return sector to Sydney. These flights were scheduled on the fifth day of a 5-day duty roster pattern for the crew.
Following a rest period in Perth of about 31 hours, the flight crew reported for duty at 0805 Western Standard Time[1]. The crew reported being adequately rested but the captain recalled having had an interrupted sleep, waking at about 0500 with a throat irritation that worsened as the day progressed.
The flight to Sydney proceeded without incident and arrived a few minutes ahead of schedule. After being on the ground for 1 hour and 17 minutes, the crew departed for Melbourne at 1733 Eastern Daylight-saving Time[2]. The captain was the pilot flying.
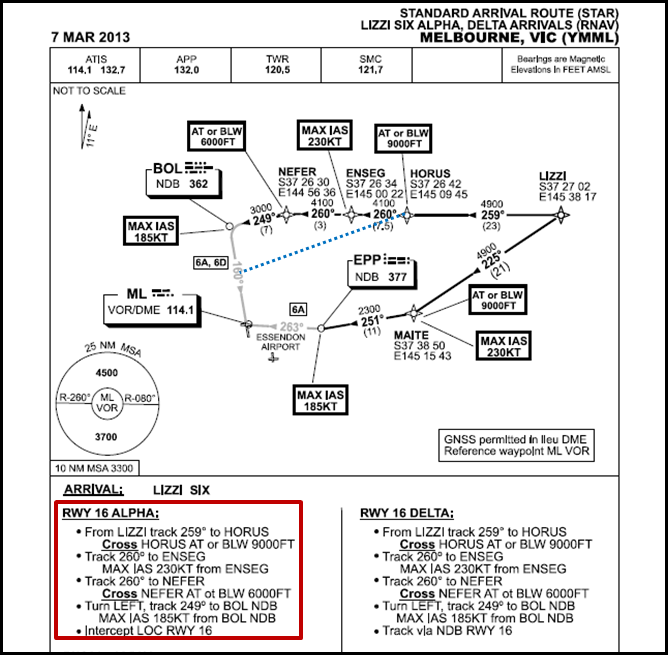
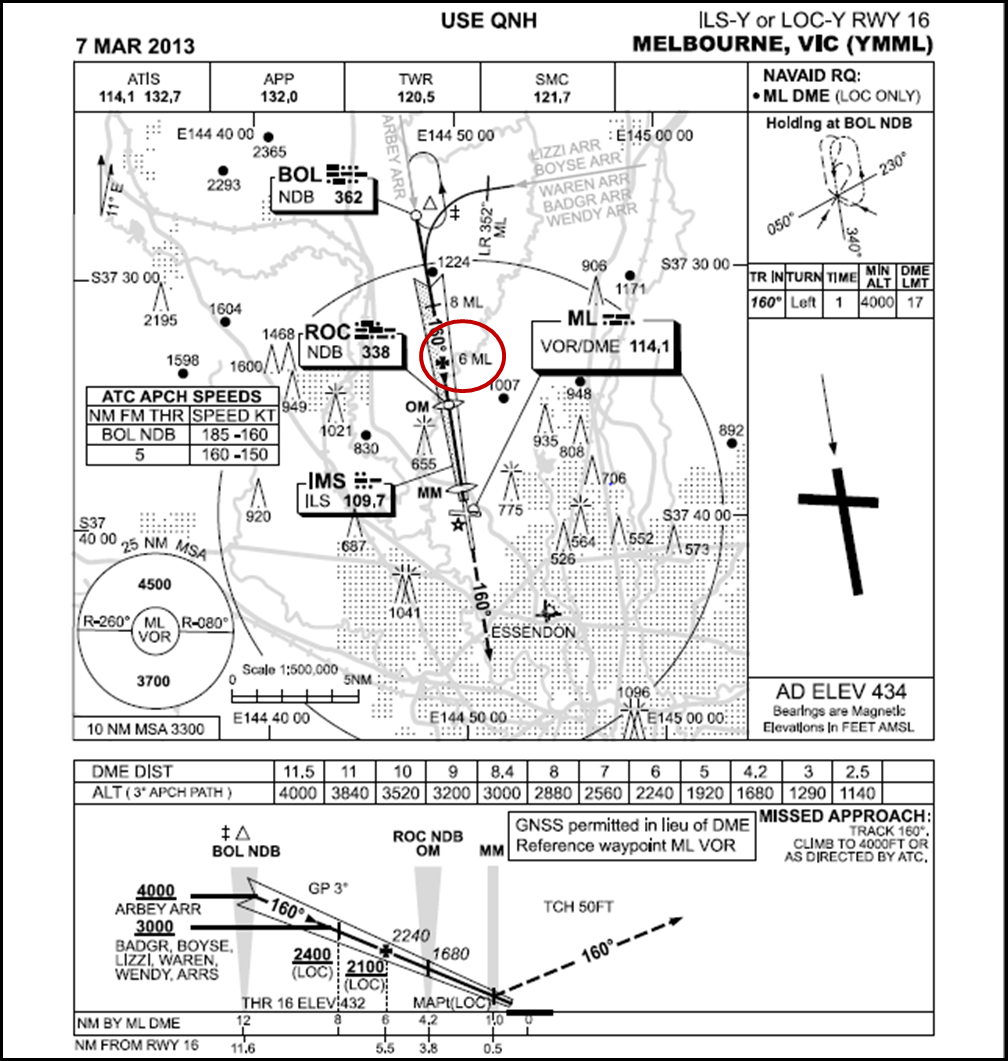
Prior to top of descent, air traffic control (ATC) cleared the crew to track via the LIZZI SIX ALPHA standard arrival route (STAR) for a landing on runway 16 (Figure 1). The crew programmed the STAR as the active flight plan in the aircraft’s auto-flight system. However, based on their previous experience operating into Melbourne Airport, and in anticipation of possible track shortening, they also programmed a secondary flight plan that would track the aircraft from waypoint HORUS to intercept the runway centreline at the final approach fix (FAF), about 6 NM (11 km) from touchdown (Figures 1 and 2). The crew conducted an arrival briefing that included the potential track shortening, and relevant speed and airspace restrictions.
Figure 1: LIZZI SIX STAR chart with anticipated track shortening (blue dotted line)
Source: Airservices Australia (edited by the ATSB)
As the crew were about to commence descent, ATC cancelled all speed restrictions, requested a high-speed descent, and advised the crew to expect track shortening. Following their acceptance of the highspeed descent request, the crew amended the programmed descent speeds and commenced descent with the auto-flight system in managed mode. In this mode the aircraft followed a pre-computed profile that allowed for aircraft deceleration and airspace restrictions along the active flight plan route.
Figure 2: Melbourne instrument landing system chart showing the location of the final approach fix (circled)
Source: Airservices Australia (edited by the ATSB)
At 1844, with the aircraft approaching 9,000 ft, ATC cleared the crew to descend to 5,000 ft and offered track shortening from HORUS (Figure 1). The crew accepted an amended track from HORUS to the FAF and activated the secondary flight plan.
The amended tracking reduced the remaining track miles to touchdown by about 5 NM (9 km). The captain recalled that after activating the secondary flight plan, the aircraft was about 1,400 ft above the recomputed profile. In response to his understanding of the aircraft’s position, the captain increased the rate of descent by selecting autoflight open descent mode and deploying half speed brake. The use of that mode, in combination with speed brake, increased the aircraft’s rate of descent to a recorded maximum of 4,000 ft/min, while maintaining the pre-programmed airspeed.
At about 1847, ATC cleared the crew to descend to 4,100 ft and asked them to report when visual. It was about 90 minutes before last light[3] and the crew could see the ground and runway but the captain stated that visibility was affected by sun glare and terrain shadowing (due to mid-level scattered cloud[4]). The crew reported visual to ATC and were cleared to descend slightly lower to 4,000 ft.
About 1 minute later, as the aircraft was approaching 4,000 ft, the auto-flight system vertical mode automatically changed from open descent to altitude capture and then to altitude hold.[5] The aircraft was now 17 NM (31 km) from touchdown with a reducing airspeed of 200 kt about 2,000 ft below a nominal 3° descent profile and 1,500 ft above the lower limit of controlled airspace. ATC cleared the crew to continue descent to 3,000 ft and the captain reselected open descent mode. The captain then instructed the first officer to activate the approach phase in the auto-flight system to enable continued deceleration towards the final approach speed.
At 1848:21, ATC asked the crew if they could accept an additional 2 NM (4 km) of track shortening direct to the Rockdale nondirectional beacon (Figure 2). The crew declined that request.
At 1848:55, ATC requested the crew to maintain an airspeed of 180 kt until turning final. The crew responded that they would endeavour to comply but advised that they would need to slow the aircraft down prior to the FAF. ATC then cleared the crew to make a visual approach, effectively allowing them to descend as required in accordance with the published visual approach procedures (see the section titled Air traffic control procedures). The aircraft was now approaching 3,000 ft and the autoflight system was in the process of capturing that altitude. At that time the aircraft was 14 NM (26 km) from touchdown, on a bearing displaced 45° from the extended runway centreline, 800 ft above the lower limit of controlled airspace and about 1,800 ft below the operator-recommended nominal 3° descent profile (see the section titled Operator procedures).
The captain set an altitude target of 1,000 ft in the flight control unit and reselected open descent mode at 1849:36. The first officer reported not hearing the captain verbalise these changes and was unaware that the altitude selector had been changed. By 1850 the crew had selected the landing gear down, the first stage of wing flap and 180 kt as the ATC-requested target speed. The descent rate increased to about 2,000 ft/min and exceeded the maximum stipulated by Qantas for a brief period.
The captain reported observing the aircraft’s instrument landing system (ILS)[6] glide slope deviation indicator on the primary flight display and that it was indicating the aircraft was above the glide slope. This appeared valid to the captain and was consistent with his earlier assessment of the aircraft being high relative to the track-shortened computed profile. Although other information about the aircraft’s flight path was available and the aircraft was not established on the ILS localiser, the captain used the glide slope deviation indicator as the primary vertical flight path guidance.
The first officer reported completing various cockpit tasks and monitoring key parameters such as track miles to run, rate of descent, speed brake use and autoflight mode during the descent. The first officer also reported monitoring the aircraft’s flight path by visual reference to the ground. From the first officer’s perspective, the approach was proceeding normally until ascertaining from the outside view that the aircraft was too low. The first officer reported checking the primary flight display noting that the aircraft profile deviation indicator confirmed the below profile state.
This prompted the first officer to advise the captain ‘You are low’, or words to that effect. In response, at 1850:30, the captain selected autoflight vertical speed mode and adjusted the vertical speed to reduce the rate of descent to about 500 ft/min. Eight seconds later, an enhanced ground proximity warning system (EGPWS) ‘TERRAIN’ alert activated when the aircraft was about 600 ft above ground level (AGL), followed by a second terrain alert. The aircraft was 9 NM (17 km) from touchdown, on a bearing displaced 30° from the runway centreline and at an altitude of 1,400 ft at that time. This was 1,900 ft below the nominal 3° descent profile and 100 ft below the lower limit of controlled airspace.
Seconds later the EGPWS generated ‘PULL UP’ aural warnings. Despite the day visual conditions, the captain decided to conduct the full EGPWS recovery manoeuvre, including disconnecting the auto-flight system, applying full back stick and selecting take-off/go-around thrust. The aircraft climbed rapidly, and the warning ceased. After the crew completed the recovery manoeuvre and levelled the aircraft at 4,000 ft, ATC vectored the aircraft for a runway 16 ILS approach. The subsequent approach and landing were normal.
The captain held an Air Transport Pilot (Aeroplane) Licence, a multiengine command instrument rating and a Class 1 Aviation Medical Certificate. The captain had a total of 21,907 hours of aeronautical experience, of which 2,272 hours were on the A330.
In the previous 90 days the captain had completed 139 hours. The captain’s most recent simulator check was on 23 February 2013.
The captain reported having a slightly sore throat in the morning that became worse during the day, particularly during the occurrence flight, and experiencing further cold symptoms following the occurrence. In addition, the captain indicated not feeling like eating, and he did not eat breakfast or lunch that day. A cup of coffee and tea were reported consumed on the trip from Perth to Sydney and a half-cup of soup on the flight from Sydney to Melbourne. The captain reported feeling tired prior to commencing duty on 8 March but self-assessed being fit for duty.
The first officer
The first officer held an Air Transport Pilot (Aeroplane) Licence, a multiengine command instrument rating and a Class 1 Aviation Medical Certificate. The first officer had a total of 10,027 hours of aeronautical experience, of which 983 hours were on the A330.
In the previous 90 days the first officer had completed 131 hours. The first officer’s most recent simulator check was completed on 10 January 2013.
The first officer reported normally obtaining 8 hours sleep each night and obtaining good sleep over this trip. On the night prior to the occurrence the first officer obtained more than 8 hours of sleep and was feeling well rested.
Recent duty
The captain and first officer were based in Sydney and were rostered for a series of flights involving multiple duty periods. On 4 March 2013, they flew from Brisbane to Perth, arriving about 1930 WST. After a rest period of about 15 hours, they flew Perth to Singapore on 5 March, arriving at 1730 WST. After a rest period of 24 hours, they flew from Singapore to Perth, arriving about 0100 WST on 7 March.
Relevant aircraft systems
Auto-flight
The A330 is equipped with an auto-flight system that controls the aircraft’s flight path according to the flight guidance mode engaged by the flight crew. The ‘managed’ mode guides the aircraft along pre-programmed route, vertical and speed profiles. In addition, there are two ‘selected’ vertical modes that guide the aircraft in response to flight path parameters selected by the crew during descent. These are open descent and vertical speed. Selected guidance always has priority over managed guidance.
The descent phase can be conducted in either managed or selected modes. In managed mode, the aircraft will be guided along a pre-computed descent profile determined by a number of factors such as altitude constraints, wind and descent speed. If the aircraft is above the computed profile, the speed will increase towards the upper limit of the speed range while maintaining engine thrust at idle. To increase the rate of descent while maintaining a target speed, flight crew should use a selected airspeed (entered in the flight control unit (FCU)) in combination with speed brake.
In either of the two selected vertical modes the aircraft descends to the altitude selected by the crew in the FCU, irrespective of any pre-programmed altitude constraints. In open descent mode, engine thrust is idle and generally results in high rates of descent. In vertical speed mode the aircraft will adopt a pitch attitude to achieve the vertical speed selected in the FCU with engine thrust varying to achieve the target airspeed.
For a descent in any of the modes, the flight management computers calculate the optimum descent profile and any subsequent deviation from that profile. The aircraft’s position relative to the computed profile is indicated on the multifunction control display unit and, when the instrument landing system (ILS) is not active, is also indicated on the primary flight display. In addition, the predicted path intercept point (assuming half speed brake extension) is indicated on the navigation display. During descent the crew can also access information about the aircraft’s flight path angle from the multifunction display.
ILS display
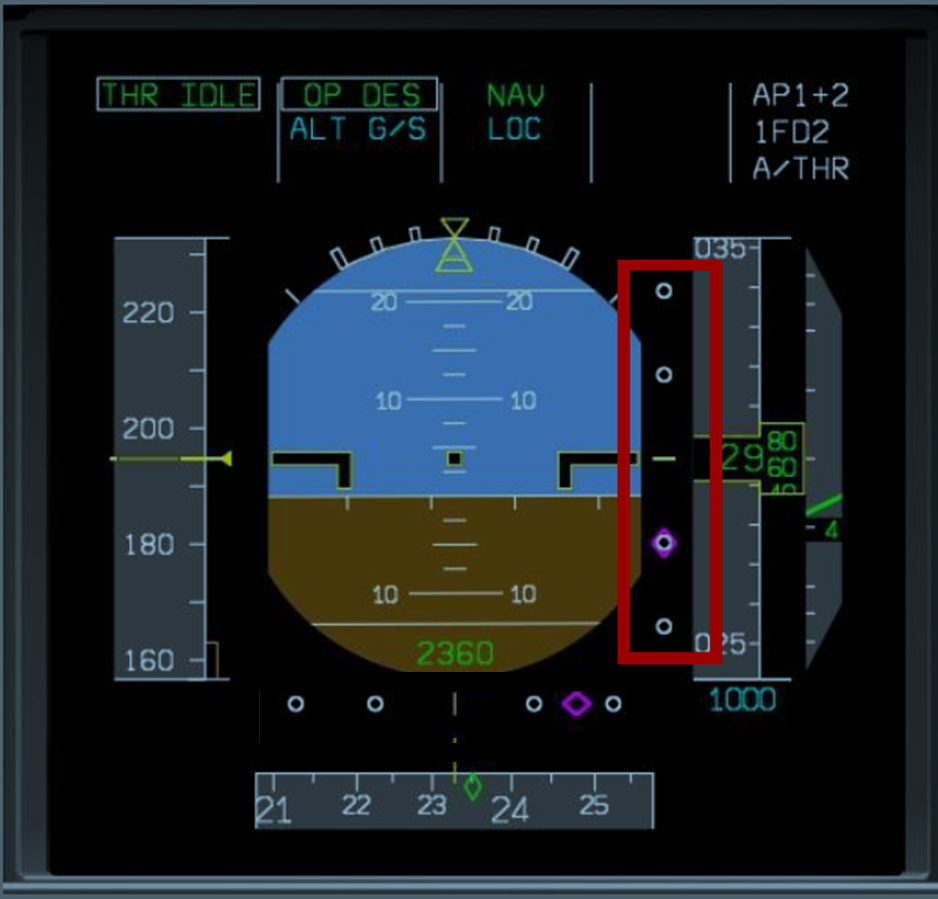
The A330 is equipped to receive and process the radio signals transmitted from a ground-based ILS facility. When these signals are available, the position of the aircraft relative to a lateral path (localiser) and vertical path (glide slope) to the runway are represented by symbols on deviation scales on each primary flight display (Figure 3).
Once the approach phase is activated, or the landing system button pushed, localiser and glide slope scales are displayed on each primary flight display. Deviation from computed profile is no longer displayed. ILS deviation symbols appear once signals are being received; however, it is possible for invalid glide slope indications to be presented on the primary flight display when the aircraft is outside of the defined coverage area.
Figure 3: A330 primary flight display with the glide slope indication scale highlighted in red
Source: Qantas
Enhanced ground proximity warning system
The A330 is equipped with an enhanced ground proximity warning system (EGPWS). The EGPWS uses aircraft inputs with onboard terrain, obstacle, and airport runway databases to predict potential conflicts between the aircraft’s flight path and terrain or an obstacle.
When the EGPWS detects a conflict ahead of the aircraft, the conflict area is shown in solid yellow or red on the navigation display. The EGPWS includes aural warnings for excessive rates of descent, excessive rates of terrain closure, and of unsafe terrain clearance when not in the landing configuration.
Air traffic control procedures
Air traffic controllers are able to issue clearances for visual approaches when flight crew have established and can continue flight to the airport with continuous visual reference to the ground or water and with visibility at least 5 km. Once an air traffic controller clears a crew to conduct a visual approach, the crew has responsibility to maintain separation from terrain and, in the case of the occurrence flight, remain at least 500 ft above the lower limit of controlled airspace.
After the occurrence, the air traffic service provider (Airservices Australia) advised that the minimum safe altitude warning system (MSAW) had been inhibited in certain areas to the northeast of Melbourne to reduce the number of false alarms in those areas. In addition, Airservices Australia advised that when a flight is cleared for a visual approach its corresponding cleared flight level is set to 000 (ft) on the controller’s air situation display. As a result, the system automatically inhibits the MSAW aural alarm and display for that flight.
Qantas procedures
Visual approach procedures
Qantas recommended its crews fly a continuous descent to touchdown at a nominal 3° profile when conducting a visual approach. While there may be slight variances, once the approach phase has been activated and the aircraft slowed (in this case, to a target speed of 180 kt), such a profile would generally approximate the flight profile generated by the flight management computers.
The only restriction on the use of open descent mode was that it was not to be used for final approach. Pilots were cautioned that open descent mode was not limited by altitude constraints, with the exception of the altitude target set in the FCU.
The procedures did not provide guidance on what altitude should be set in the FCU during a visual approach not involving a circuit. The captain later reported that the usual practice was to set a safe altitude as a limitation. The guidance regarding visual circuits did not include any reference to setting an altitude target in the FCU in case of a visual circuit, such as the 1,000 ft set by the captain in this case.
In addition, the procedures specified that during visual procedures both pilots were ‘head free’. This allowed pilots to monitor external references as well as instruments, placing increasing emphasis on external visual cues as the aircraft progressed down the approach path. Qantas highlighted the importance of flight crew members being continuously aware of the intent of the pilot flying and the procedure nominated, and monitor that the aircraft was being operated in accordance with that procedure. If a procedure was not being adhered to or the aircraft deviated from the intended flight path, the pilot not flying was advised to immediately advise the pilot flying.
Maximum rates of descent
Maximum permitted descent rates were specified for operating the aircraft between 5,000 ft and 1,000 ft above ground level (AGL), such that the rate of descent was not greater than the aircraft’s height above terrain. For example, when passing 2,000 ft, the rate of descent was limited to 2,000 ft/min. If excessive rates of descent were detected, the pilot not flying was required to call ‘Rate of Descent’ and the pilot flying acknowledge and adjust accordingly. The reduction to the permitted descent rate as the aircraft’s height reduced was to ensure increased recognition and response times in the event of an unintentional conflict with terrain. In this case, when the aircraft was descending below 2,000 ft AGL, the rate of descent was generally higher than that permitted. During the descent through 1,000 ft AGL the rate of descent was 1,900 ft/min.
EGPWS procedures
The procedure relating to activation of the EGPWS ‘PULL UP’ warning required the crew to simultaneously disconnect the auto-flight system, pitch the aircraft up to the full back stick position and select take-off/go-around thrust, confirm speed brake retraction and adopt a wings level attitude. For operations during daylight visual conditions, with terrain and obstacles clearly in sight, the alert could be considered cautionary; however, positive action was to be taken until the alert stopped or a safe flight path was assured. The crew’s actions in response to the warnings generated were consistent with the procedures.
Use of the ILS
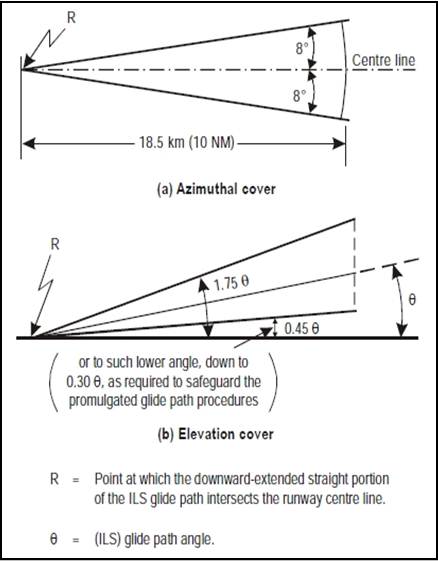
The use of ILS glide slope indications when an aircraft was displaced from the approach centreline was not specifically addressed in the Qantas procedures. However, a note in the standard operating procedures for conducting an ILS approach highlighted the International Civil Aviation Organization (ICAO)-defined envelope where the quality of the glide slope signal ensured a normal capture. This envelope was within 10 NM (18.5 km) and 8° either side of the glide path centre-line, and within a small range of elevation (Figure 4 – diagram not included in the Qantas procedures). The note indicated that when arming the approach well outside of the normal glide slope capture envelope, a spurious glide slope engagement may occur due to a wrong glide slope deviation signal. Whenever a pilot noticed any spurious indications, it was stipulated that the autoflight system and approach mode be disengaged and recommended that any subsequent rearming of the approach mode occur within the normal capture zone.
Figure 4: ILS glide slope coverage
Source: ICAO Annex 10
Internal review of visual approach procedures
A Qantas investigation of this occurrence identified that:
Qantas Airlines provide limited guidance on how a visual approach should be flown and the briefing required for the conduct of the approach to enable the Flight Crew to have a shared mental model.
That conclusion was consistent with the report from the first officer that there was no requirement for the visual approach brief to include detail of the intended autoflight system mode selections.
Previous occurrences
A review of the ATSB occurrence database identified a number of other incidents where the aircraft was descended below the normal approach profile, resulting in the infringement of the minimum altitude requirements and, in some cases, activation of the EGPWS. These occurrences each involved the operation of the auto-flight system in open descent mode (or the equivalent ‘flight level change’ mode for occurrences involving Boeing aircraft), without an altitude target.
A number of ATSB investigations into those occurrences are summarised in the following discussion.[7]
On 4 November 2007, a Boeing 777-2D7 (777) aircraft, registered HS-TJW, was being operated by Thai Airways International Ltd (Thai Airways) on a scheduled passenger service from Bangkok, Thailand to Melbourne, Victoria with 17 crew and 277 passengers on board. During the conduct of a nondirectional beacon (NDB)[8] non-precision approach to runway 16 at Melbourne Airport in flight level change mode, the crew descended the aircraft below a segment minimum safe altitude. Soon after, the crew received two EGPWS cautions. At that time, the crew became visual with the ground below and the Melbourne aerodrome controller observed the aircraft 'unusually low for an aircraft'. The crew levelled the aircraft and made a visual approach and landed on runway 16.
The ATSB found that the aircraft descended below a critical altitude during the NDB approach and that the crew did not monitor the aircraft's progress correctly during the NDB approach.
Thai Airways had known about the difficulties in flying approaches without constant angle approach paths and was in the process of training flight crews on procedures specific to NDB approaches when the incident occurred. In October 2007, Thai Airways introduced a training program to instruct pilots on a new method to conduct those approaches. At the time of the incident, the pilots of the 777 had not undergone that training.
On 4 and 29 May 2010, an Airbus A330-343E aircraft, registered 9M-XXB, was being operated by AirAsia X on scheduled passenger services from Kuala Lumpur, Malaysia to the Gold Coast, Queensland. On both occasions, there was low cloud and reduced visibility on arrival at the Gold Coast.
During non-precision instrument approaches conducted at Gold Coast Airport on both days, the flight crews descended the aircraft below the segment minimum safe altitudes and outside controlled airspace while using open descent mode. As a result, there was no longer separation assurance from terrain and aircraft operating outside controlled airspace.
While those operational non-compliances occurred prior to the final approach fix for the instrument approaches and not below 1,200 ft above aerodrome height, they were indicators of a minor safety issue regarding AirAsia X training of its flight crews.
In response to this incident, AirAsia X made a number of changes to flight crew procedures when conducting instrument approaches. In addition, the recurrent simulator training program was modified to include more complex non-precision instrument approaches.
At 2019 Eastern Standard Time[9] on 24 July 2011, a Thai Airways Boeing 777-3D7 aircraft, registered HS-TKD, was conducting a runway 34 VOR[10] approach to Melbourne Airport, Victoria. During the approach, the tower controller observed that the aircraft was lower than required and asked the flight crew to check their altitude. The tower controller subsequently instructed the crew to conduct a go-around. However, while the crew did arrest the aircraft’s descent, there was a delay of about 50 seconds before they initiated the go-around and commenced a climb to the required altitude.
The ATSB established that the captain may not have fully understood some aspects of the aircraft’s automated flight control systems and probably experienced ‘automation surprise’ when the aircraft pitched up to capture the VOR approach path. As a result, the remainder of the approach was conducted using the autopilot’s flight level change mode. In that mode the aircraft’s rate of descent is unrestricted and therefore may be significantly higher than that required for an instrument approach. In addition, the flight crew inadvertently selected a lower than stipulated descent altitude, resulting in descent below the specified segment minimum safe altitude for that stage of the approach and the approach not being managed in accordance with the prescribed procedure.
On 16 July 2012 at about 0830 New Zealand Standard Time[11], an Airbus A320-232 aircraft, registered VH-VQA and operated by Jetstar Airways (Jetstar), was conducting an Area Navigation (Required Navigation Performance) approach to runway 05 at Queenstown, New Zealand. During the approach the aircraft descended below two segment minimum safe altitudes. Upon recognising the descent profile error, the crew climbed the aircraft to intercept the correct profile and continued the approach to land.
The ATSB found that, contrary to their intentions, the flight crew continued descent with the autoflight system in open descent mode, which did not provide protection against infringing the instrument approach procedure’s segment minimum safe altitudes. The ATSB also found that the flight crew was not strictly adhering to Jetstar’s sterile flight deck procedures, which probably allowed them to become distracted.
The ATSB found that the Jetstar procedures did not specifically draw the flight crew’s attention to unchanged auto-flight system modes during descent or prompt crew reconsideration of the most suitable descent mode at any point during descent. Additionally, the Jetstar’s procedures allowed the crew to select the altitude to which they were cleared by air traffic control on the flight control unit altitude selector, irrespective of intervening altitude constraints. This combination of procedures provided limited protection against descent through segment minimum safe altitudes.
While the flight crew was conducting a visual approach and tracking to intercept final approach, the aircraft descended about 1,900 ft below the nominal 3° descent profile to about 600 ft above ground level (AGL), activating the aircraft’s enhanced ground proximity warning system (EGPWS). Shortly before that alert, the crew had identified that the aircraft was low and were in the process of responding when the EGPWS activated. The crew conducted an EGPWS recovery manoeuvre followed by a routine instrument approach and landing. The following analysis will examine the factors that contributed to the abnormal descent, which led to the EGPWS warning, and review the risk controls as they apply to visual approaches.
Abnormal flight path
The significant descent below the intended flight path was consistent with degraded flight crew situation awareness for a period during the visual approach.
Situation awareness is a human perceptual state in which information is gained from the environment through a number of processes. These processes are believed to be the perception of environmental elements, the comprehension of their meaning and the projection of their status following a change in a variable (such as time) (Endsley, 2005). For a visual approach the available cues include visual reference to terrain, track distance to the next waypoint or touchdown, flight path vector on the primary flight display (deviation from the nominal approach path), multifunction control display unit profile indication and barometric and radio altimeter indications. In addition, within the specified coverage of the instrument landing system (ILS), the localiser and glide slope indications can be used.
After accepting track shortening, the captain assessed that the aircraft was above the recomputed profile. As a result, the captain selected open descent mode and half speed brake to increase the descent rate. This resulted in a higher than normal descent rate and, by continuing in open descent mode, the aircraft’s descent was only constrained by the altitude target selected in the flight control unit (FCU).
It was crucial, then, for the crew to maintain an increased awareness of the aircraft’s flight path relative to the computed profile and controlled airspace restrictions. However, it appears that the crew did not maintain that awareness because the aircraft subsequently descended significantly below profile until the EGPWS warnings at 1851.
Both pilots were expected to monitor the flight path and ensure that the trajectory and energy of the aircraft, current and projected, conformed to the planned approach. The first officer, as pilot not flying, reported monitoring the flight path during the approach. It is not clear if the first officer noticed that the aircraft was below profile during the latter stages of the approach but the captain, who was the pilot flying, was not advised that the aircraft was ‘low’ until just before the EGPWS warning.
The captain observed that the ILS glide slope indications were active and indicating that the aircraft was above the glide slope, which was consistent with his expectation. As a result, the captain considered the glide slope indications to be valid and useful for flight path guidance. Subsequently, the captain focussed on the glide slope without any apparent reference to the other available flight path or profile information.
Glide slope indications outside of the specified coverage area were unreliable and therefore an invalid source of flight path guidance. In addition, even if the signal was valid, following a glide slope indication with more track miles to fly than the straight-line distance to the glideslope antenna would, with reference to the track miles to run, result in a shallower flight path than the nominal 3° profile. Reference by the crew to the other available cues during the visual approach would have increased the likelihood of them detecting that the aircraft was below profile.
When cleared for the visual approach, the captain set 1,000 ft in the FCU, which although permitted by the manufacturer and operator, was well below the altitude of about 2,200 ft required to intercept the final approach path at a nominal 3° profile. Although the reason for the FCU setting by the captain could not be determined, the effect was that, in the open descent mode, the aircraft would descend to within 550 ft AGL unless the crew intervened. Selection of a more appropriate altitude target would have provided an effective defence in the event of degraded situation awareness.
Although the aircraft was about 1,900 ft below profile on receipt of clearance for the visual approach, the descent was continued in a high drag configuration using open descent mode until the first officer announced that the aircraft was low. The captain then selected vertical speed mode to reduce the aircraft’s rate of descent; however, this did not prevent activation of the EGPWS alerts and subsequent warning.
In summary, the flight crew’s situation awareness during the visual approach was adversely affected by the captain’s focus on the glide slope indication and the crew not recognising and communicating the deviation from the nominal descent profile until the aircraft was approaching about 1,300 ft AGL.
Fatigue and related factors
Fatigue can have a range of adverse influences on human performance, such as slowed reaction time, decreased work efficiency, reduced motivational drive, increased variability in work performance, and more lapses or errors of omission (Battelle Memorial Institute 1998). In addition, most people generally underestimate their level of fatigue.
Sleep is vital for recovery from fatigue, with both the quantity and quality of sleep being important. It is generally agreed that most people need at least 7 to 8 hours of sleep each day to achieve maximum levels of alertness and performance. Some research has concluded that less than 5 hours sleep in the previous 24 hours is inconsistent with a safe system of work (Dawson and McCullough 2005) whereas other research has shown that having less than 6 hours sleep affects performance (Thomas and Ferguson 2010, Williamson and others 2012).
The captain
The captain reported feeling tired on the morning of the occurrence and during the afternoon of the occurrence flight. He had 6 hours disrupted sleep the night before the occurrence, and his previous sleep, of about 6.5 hours, occurred outside his normal circadian low. Although time awake, time of day when the occurrence happened and workload did not appear noteworthy, the captain reported having a sore throat and cold symptoms during the day. There appeared to be no concerns regarding the length of the time between duty periods or the standard of accommodation.
The captain also reported having very little nutrition on the day of the occurrence, including no breakfast or lunch. Research has provided inconsistent results regarding the effects of missed meals on performance. However, Barshi and Feldman (2012) have recently concluded that low blood sugar due to a lack of food has a range of effects on cognitive performance, and the effects are often significantly underestimated (see also Feldman and Barshi 2007). It is also widely accepted that regular nutrition is an important fatigue countermeasure.
In summary, the captain was experiencing the effects of recent restricted and disrupted sleep, a cold/virus and limited nutrition. It is reasonable to conclude that the combination of these factors probably reduced the captain’s capability to perform during the occurrence flight. However, it was difficult to establish the level of reduction or the extent to which it may have influenced the captain’s actions during the occurrence, and there were no indications that the captain’s performance was actually affected prior to the occurrence.
The first officer
In relation to the first officer, there were no indicators of fatigue and the late communication of the descent profile deviation may have been associated with the general human factors limitations that counter effective flight path monitoring. These limitations are discussed in the following section.
Flight path monitoring
As this and other occurrences have shown, flight path monitoring is subject to a number of challenges or barriers related to human factors limitations and has recently been the focus of several industry working groups and related research. The findings from these working groups and studies highlight the various human performance limitations that are detrimental to effective monitoring.
Dismukes and Berman (2010) showed that although checklists and flight crew monitoring are important defences, and in the vast majority of cases are performed appropriately, they do not always catch flight crew errors and equipment malfunctions. They also noted:
…even though automation has enhanced situation awareness in some ways, such as navigation displays, it has undercut situation awareness by moving pilots from direct, continuous control of the aircraft to managing and monitoring systems, a role for which pilots are poorly suited. Also, the very reliability of automation makes it difficult for pilots to force themselves to “stay in the loop”. Research is needed to develop ways to help pilots stay in the loop on system status, aircraft configuration, flight path, and energy state. These new designs must be intuitive and elicit attention as needed, but minimize effortful processing that competes with the many other attentional demands of managing the flight.
The United States Flight Safety Foundation (FSF) Active Pilot Monitoring Working Group has developed a practical guide to improving flight path monitoring (Flight Safety Foundation, 2014). The guide listed four general human factors limitations that adversely affect monitoring:
The human brain has difficulty with sustained vigilance
The human brain has quite limited ability to multitask
Humans are vulnerable to interruptions and distractions
Humans are vulnerable to cognitive limitations that affect what they notice and do not notice.
A number of other factors were identified that could inhibit effective flight path monitoring. These included time pressure, lack of feedback to pilots when their monitoring lapses, the design of flight deck systems and procedures, inadequate mental models of auto-flight system modes and a lack of organisational emphasis and practical guidance on monitoring.
The Dismukes and Berman study also examined monitoring deviations and found those relating to ‘not monitoring aircraft state or position’ were the least frequent, at 17 per cent. The most common type was a late or omitted call (such as ‘1,000 [ft] to go’), followed by omitted verification of system status. Of interest to this occurrence, the authors found that ‘some deviations are clearly unintentional, such as deviations from flight path’. The authors went on to state that ‘given the large numbers of opportunities for deviation, the deviation rates were probably well below one percent’ and ‘…the vast majority of deviations had no observable outcome’.
The United Kingdom Civil Aviation Authority (CAA) formed a Loss of Control Action Group to examine and provide guidance on, among other things, the development of pilot monitoring skills. The resulting guidance emphasised the importance of ‘a structured and interactive briefing’ which ‘…provides the crew with an opportunity to: share a common action plan; and set priorities and share tasks…’ including the need to ‘brief the plan for energy management with altitudes and minimum approach gates’.
The FSF working group, the CAA action group and the study by Dismukes and Berman (details of which are available in the section titled Sources and submissions) each made a number of recommendations and suggestions in the areas of monitoring practices, policy and procedures, auto-flight system monitoring and training and evaluating monitoring skills. Pilots and operators may benefit from a review of this advice.
The ATSB did not identify any specific factors that adversely affected the first officer’s ability to monitor the flight path. However, it is likely that the first officer was not expecting or aware of the captain’s use of the ILS glide slope information as the primary reference for flight path guidance. In addition, the first officer did not recall hearing the captain verbalise the selection of 1,000 ft in the FCU. While the first officer should have been able to independently monitor the approach using other valid information, it was apparent that the crew did not have a shared mental model of how the approach would be flown. The absence of a shared mental model increased the risk that the first officer would not identify and respond appropriately to the captain’s actions. It is also possible that the general limitations of human monitoring capability discussed above may have influenced the first officer’s performance.
Approach procedures
This occurrence demonstrates the risks associated with using ILS glide slope indications for primary navigation reference outside of the specified coverage area. Integration of other available external and internal cues enhances situation awareness and reduces those risks.
The crew’s selection of autoflight open descent mode during the latter stages of the approach, combined with the high drag configuration, generated a high rate of descent close to the ground without altitude constraints or an effective FCU altitude target. Although Qantas allowed the use of open descent mode during visual approaches, this selection increased the risk of high rates of descent and inadvertent descent below minimum altitude requirements.
One of the risk controls that can be used during an approach is to set an FCU target altitude that provides assurance that the aircraft’s descent path is appropriately constrained. Had the crew set 2,200 ft as the target altitude in the FCU for arrival overhead the final approach fix, the aircraft’s auto-flight system would have captured that altitude prior to the fix and provided an opportunity for the crew to recognise that the aircraft was below the nominal descent profile.
Operators may benefit from considering the adequacy of their guidance on how FCU target altitude selections should be used during visual approaches. Such guidance would reduce the risk of inadvertent descent below the intended flight path.
Findings
From the evidence available, the following findings are made with respect to the flight path management and ground proximity warning involving Airbus A330, registered VH-EBV and operated by Qantas Airways Limited (Qantas), that occurred 15 km north-east of Melbourne Airport, Victoria on 8 March 2013. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
During the latter stages of a visual approach the captain assessed the aircraft’s flight path using glide slope indications that were not valid, resulting in an incorrect assessment that the aircraft was above the nominal descent profile.
The combination of the selection of an ineffective altitude target while using the autoflight open descent mode and ineffective monitoring of the aircraft’s flight path resulted in a significant deviation below the nominal descent profile.
The flight crew’s action to reduce the aircraft's rate of descent following detection of the altitude deviation did not prevent the aircraft descending outside controlled airspace and the activation of the enhanced ground proximity warning system.
Other factors that increased risk
Qantas provided limited guidance on the conduct of a visual approach and the associated briefing required to enable the flight crew to have a shared understanding of the intended approach. [Safety issue]
The captain’s performance capability was probably reduced due to the combined effects of disrupted and restricted sleep, limited recent nutrition and a cold/virus.
Other findings
The flight crew acted to reduce the aircraft's rate of descent prior to the activation of the enhanced ground proximity warning system (EGPWS) and conducted a recovery manoeuvre immediately after the EGPWS ‘PULL UP’ warning.
Safety issues and actions
The safety issue identified during this investigation is listed in the Findings and Safety issues and actions sections of this report. The ATSB expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Where relevant, these safety issues and actions will be updated on the ATSB website as information comes to hand. The initial public version of these safety issues and actions are in PDF on the ATSB website.
Visual approach guidance
Qantas provided limited guidance on the conduct of a visual approach and the associated briefing required to enable the flight crew to have a shared understanding of the intended approach.
The sources of information during the investigation included the:
flight crew and operator of VH-EBV
aircraft flight data recorder
aircraft manufacturer
Airservices Australia (Airservices).
References
Barshi, I & Feldman, J 2012, ‘The safety and ethics of crew meals’, in W Karwowski (Ed.) Advances in Human Aspects of Aviation, CRC Press, pp. 472-480.
Battelle Memorial Institute, 1998, An Overview of the scientific literature concerning fatigue, sleep, and the circadian cycle, Report prepared for the Office of the Chief Scientific and Technical Advisor for Human Factors, US Federal Aviation Administration.
Dawson, D & McCulloch, K 2005, ‘Managing fatigue: It’s about sleep’, Sleep Medicine Reviews, vol. 9, pp. 365-380.
Dismukes, RK & Berman, B 2010, Checklists and monitoring in the cockpit: Why crucial defences sometime fail, National Aeronautics and Space Administration Technical Memorandum NASA/TM2010216396.
Endsley, M. R. 1995. ‘Toward a theory of situation awareness in dynamic systems.’ Human Factors, vol. 37(1), pp 32-64.Feldman, J & Barshi, I 2007, The effects of blood glucose levels on cognitive performance: A review of the literature, NASA Technical Memorandum TM2007214555.
Flight Safety Foundation 2014, A Practical Guide for Improving Flight Path Monitoring: Final report of the Active Pilot Monitoring Working Group.
Thomas, M. J. W. & Ferguson, S.A. 2010, ‘Prior sleep, prior wake, and crew performance during normal flight operations’, Aviation, Space, and Environmental Medicine, vol. 81, pp. 665-670.
United Kingdom Civil Aviation Authority 2013, Monitoring Matters: Guidance on the Development of Pilot Monitoring Skills, CAA Paper 2013/02.
Williamson, A Lombardi, Folkard DA, Stutts, S. Courtney, J. T.K. & Connor, J.L. 2011, ‘The link between fatigue and safety’, Accident Analysis and Prevention, vol. 43, pp. 498-515.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the flight crew and operator of VH-EBV, the Bureau d’Enquêtes et d’Analyses pour la sécurité de l'aviation civile (BEA), the aircraft manufacturer, Airservices and the Civil Aviation Safety Authority.
Submissions were received from the flight crew and operator of VH-EBV, the BEA, the aircraft manufacturer, Airservices and the Civil Aviation Safety Authority. The submissions were reviewed and where considered appropriate, the text of the draft report was amended accordingly.
Appendices
Appendix A – VH-EBV flight data recorder and enhanced ground proximity cautions, alerts and warnings
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.