Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
At about 0625 local time on 6 September 2025, the pilot and sole occupant of a Robinson R22 helicopter departed Cloncurry Airport, Queensland, to conduct commercial aerial mustering operations about 100 km north of Cloncurry. At about 0830 the pilot identified a small mob of cattle under trees in a dry creek bed. Attempting to move the stock, the pilot turned the aircraft downwind and recalled the aircraft descended during the turn. While attempting to arrest the rate of descent the pilot increased power as they attempted to avoid a dead tree which they estimated was about 6–8 m high. However, as the aircraft was already at maximum power the pilot was unable to gain sufficient height and the helicopter collided with the tree.
The pilot recalled the tree penetrated the windscreen and that the helicopter began to rotate. The helicopter then impacted terrain on its left side, temporarily rendering the pilot unconscious. The aircraft came to a stop in a dry creek bed about 20 m from the impact tree. The helicopter sustained substantial damage: the tail rotor and horizontal stabiliser separated from the main fuselage during the accident sequence and were located in close proximity to the tree (Figure 1).
Figure 1: Occurrence aircraft
Source: LifeFlight, modified by the ATSB
After regaining consciousness, the pilot recalled they were held in their seat by the seatbelt and freed themselves from the wreckage. They contacted nearby ground crew on motorcycles via two-way radio to request assistance. The operator advised that the onboard tracking and phone records showed the pilot then called the operator about 15 minutes after the impact with the tree.
The pilot had been wearing a helmet which sustained minor damage. The pilot sustained serious injuries that included cracked vertebrae and was airlifted to Mount Isa hospital later that morning.
The 2014 CASA aerial mustering sector risk profile identified some of the key risks during aerial mustering operations stating:
The aerial mustering sector is hazard rich due to the inherent characteristics of the operation, such as very low level flying, high workload, negative effects from weather, obstacles such as power lines, trees, and terrain, pilot distraction, small power margins, and extended time operating within the shaded area of the height/ velocity diagram (‘deadmans curve’). In some parts of Australia, military aircraft may intrude into airspace above cattle stations which could cause airborne conflict. Pilot training, supervision and mentoring play an important role in developing pilot skills to manage aerial mustering manoeuvres.
Safety message
Aerial stock mustering involves operating in an inherently hazardous environment – aircraft are manoeuvred at very low level, close to obstacles. Low‑level operations in small helicopters often result in minimal available power margins because reduced airspeeds and abrupt manoeuvring of the helicopter both require additional power. When the helicopter’s power required is greater than the power available, the aircraft is unable to maintain height and can cause the pilot to attempt to apply additional collective[1] pitch. The result is a reduction in rotor RPM and therefore further loss of altitude. Also, low‑level flight reduces the time available for pilots to apply corrective techniques to restore rotor RPM and level flight.
Several Robinson Helicopter Safety Notices discuss the risks involved with low rotor RPM and are available on its website robinsonheli.com.
Operators and pilots of Robinson R22 and other smaller helicopters, especially those used for low-level aerial work such as mustering, are encouraged to review the causes, effects and recovery techniques for low rotor RPM and ensure they avoid low rotor RPM situations at low level in environments where obstacles may present a significant hazard.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
[1]The collective control changes the pitch angle of all main rotor blades.
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On the morning of 3 September 2025, a Eurocopter AS 350 was conducting agricultural spraying operations in the Holbrook, New South Wales, area.
In preparation for the second run for the day, the pilot conducted a hazard reconnaissance of a 14‑hectare paddock and identified wires to the west, a road to the east and livestock in the corners of neighbouring paddocks.
The helicopter was fitted with a GPS navigational system which also featured a wire detection system designed to alert the pilot when the aircraft is approaching a mapped wire. The wire was correctly mapped in the aircraft GPS system.
Once spraying operations had commenced, the pilot reported that they were focusing on the spray as well as the stock in the neighbouring property which was at the end of their run. This resulted in them losing sight of the already identified wires in the spraying run overshoot area. Shortly after the dispensing had been completed, the pilot entered the neighbouring paddock and saw the wires. However, with little time to respond, the helicopter’s skids struck a wire resulting in damage to the tail rotor. The helicopter then began vibrating violently and rotated to the left, entering multiple 360° turns before it collided with terrain, rolled onto its right side and caught fire. The pilot was able to exit the passenger door of the helicopter and sustained minor burn injuries. The helicopter was destroyed by post-impact fire (Figure 1).
Figure 1: Post-impact damage
Source: NSW Police
Safety message
Despite the hazard assessment and the systems in place to warn about the wires, in this occurrence the distraction of the stock in the neighbouring paddocks diverted the pilot’s attention resulting in them losing sight of the wires.
Research by the ATSB has shown that 63% of pilots were aware of the position of the wire before they struck it.[1]
In association with the Aerial Application Association of Australia (AAAA), the ATSB released an educational booklet, Wirestrikes involving known wires: A manageable aerial agriculture hazard (AR-2011-028). This booklet contains details of multiple wirestrike accidents, lessons learned, and a number of strategies to help agricultural pilots manage the ongoing risk of wirestrikes during spraying operations. The booklet notes that focusing attention on non‑operational tasks or focusing on operational tasks at the wrong time can affect pilots’ hazard avoidance, detection and reaction times, and that all pilots, no matter the level of experience, can get distracted.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
[1]ATSB research and analysis report B2005/0055, Wire-strike Accidents in General Aviation: Data Analysis 1994 to 2004, available at www.atsb.gov.au.
The ATSB is assisting Gliding Australia with an investigation into a collision with terrain involving Alexander Schleicher AS 33 Me, registration VH-8SP, near McCaffrey Field, Queensland, on 30 July 2025.
During glider towing operations, after the glider was released, it collided with terrain, resulting in fatal injuries to the pilot.
In response to this accident, Gliding Australia commenced an investigation. As part of its investigations, Gliding Australia requested technical assistance from the ATSB to examine components from the accident.
To facilitate this support and to provide the appropriate protections for the information, the ATSB initiated an investigation under the Transport Safety Investigation Act 2003.
Any enquiries relating to the investigation should be directed to Gliding Australia.
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 19 August 2025, a Cessna 180 with a tailwheel landing gear was approaching runway 20 at Borroloola Aerodrome, Northern Territory, in variable, moderate crosswind conditions. There were 2 pilots and 1 passenger on board. Just after touchdown, the aircraft turned into the wind and started to veer left off the runway. The pilot in command initiated a go-around and as the aircraft began to lift off, it continued drifting off the runway.
The left wheel struck a mound of dirt beside the runway and the wheel departed the aircraft, causing the aircraft to rotate, collide with the ground and skid sideways, subsequently striking a concrete culvert before coming to rest (Figure 1). The aircraft was substantially damaged during the accident, however the 3 people on board were uninjured.
Figure 1: Aircraft damage
Source: Borroloola Aerodrome operator
Safety message
This accident provides a reminder for pilots to be prepared to conduct a missed approach, particularly in tailwheel aircraft during crosswind conditions. Tailwheel aircraft have less directional stability on the ground due to the location of the centre of gravity behind the main wheels. They are more susceptible to the effects of crosswind and the tail can have a tendency to swing sideways on the ground. They require more active input to maintain directional control and any yaw needs to be corrected immediately as it can quickly lead to a large swing and potential loss of control. If conditions during approach are challenging, an early go-around can provide an opportunity to reassess the landing options and make a reasoned decision about whether to attempt another approach and plan for how to manage the conditions.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 14 August 2025, a Just Aircraft SuperSTOL XL amateur-built aircraft departed from Weipa, Queensland, for a flight to Cooktown. The pilot was the sole person on board and the flight was planned to proceed via Coen with a subsequent refuelling stop, if required, using fuel carried in a container on board the aircraft. After leaving Coen, the pilot determined that refuelling was required and selected an off-airfield landing location near Bathurst Bay where, after an aerial inspection of the selected area, the pilot made an uneventful landing at the mouth of a river.
At around 1630, after refuelling and having inspected the intended take-off strip area for suitability, the pilot commenced the take-off. The pilot later reported that, shortly after clearing the ground, the aircraft encountered a strong crosswind gust from the left and the aircraft yawed forcefully into the wind. Directional control and climb performance of the aircraft was rapidly lost and the pilot ditched the aircraft in the shallow river to the left of the strip end (Figure 1). The pilot was uninjured and able to evacuate the aircraft and swim to the shore, however the aircraft became partially submerged (Figure 2) and was substantially damaged by water ingress.
Figure 1: Overview of take-off strip and accident location
Source: Google Earth, annotated by the ATSB
Figure 2: Aircraft final location after being moved by incoming tide, partially submerged
Source: Pilot supplied
Safety message
Take-offs and landings away from established aerodromes and aircraft landing areas (ALAs) can present challenges and significantly increased risks for operating crew. In this instance, while the pilot was operating an aircraft designed and equipped for such off‑field work, the presence of obstacles and hazards close to the chosen strip reduced the options available to the pilot for a safe recovery or landing after the wind gusts and controllability issues were encountered.
Pilots should also consider the shielding effects of any elevated terrain surrounding planned take-off areas and consider the potential effects of abrupt wind changes and windshear once the aircraft outclimbs the terrain.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence summary
Mode of transport
Aviation
Occurrence ID
AB-2025-040
Occurrence date
14/08/2025
Location
155 km north-west of Cooktown Airport
State
Queensland
Occurrence class
Accident
Aviation occurrence category
Collision with terrain, Loss of control, Weather - Other
The ATSB is investigating a collision with terrain involving an Air Tractor AT-802, registration VH‑ODX, 17 km north of Cummins Town aerodrome, South Australia, on 8 September 2025.
During aerial agricultural spraying operations, the aircraft collided with terrain resulting in substantial damage. The pilot was fatally injured.
To date, the ATSB has examined the site and wreckage, conducted interviews, collected documentation, and recovered recorded data from the accident flight.
A preliminary report, which detailed factual information established during the evidence collection phase, was released on 23 October 2025 (see below).
The final report has been drafted and is undergoing internal review to ensure the report adequately and accurately reflects the evidence collected, analysis, and agreed findings.
The final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.
Last updated:
Preliminary report
Report release date: 23/10/2025
This preliminary report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On 8 September 2025, at about 0937 local time, the pilot in command (and sole occupant) of an Air Tractor AT‑802A agricultural aircraft, registered VH‑ODX and operated by Aerotech Australasia,[1] departed from the Cummins Town aerodrome, South Australia. The pilot ferried the aircraft to a private airstrip approximately 22 km to the north that was to be used as a supply point for the day’s aerial spraying activities.
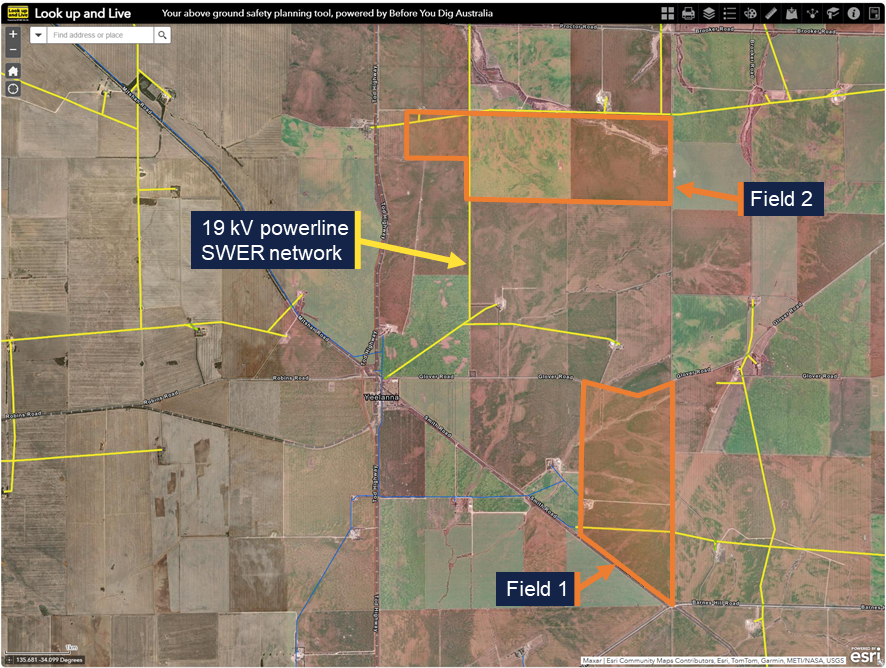
Having diverted slightly right of the direct track to overfly the first field to be sprayed that morning, the pilot arrived at the supply airstrip at 0946 where they were met by the loader.[2] The tasking for the day was the aerial application of 13 loads of fungicide and insecticide across 2 wheat fields (‘Field 1’ and ‘Field 2’ in Figure 1).
The aircraft was loaded with chemical and, at 1005, the flight departed for application of the first load in a field about 11 km to the south‑south‑east. Recorded data from the aircraft identified the field was sprayed in a north‑south racetrack pattern[3] until the hopper was emptied, before returning to the supply airstrip. This operation was repeated 3 times.
Electrical powerlines spanned the fields of the property being sprayed. The first field featured a 19 kV single‑wire earth return powerline crossing the southern section in an east‑west direction (Figure 1 and Figure 2). The data showed that the pilot flew mostly under this powerline but occasionally flew over it where there was a power pole, or, where the powerline merged close to the edge of the field.
Figure 1: Fields that were sprayed (outlined in orange) and the surrounding powerline network (yellow lines)
SWER – Single‑wire earth return. Source: Look up and Live website, annotated by the ATSB
Figure 2: 19 kV single-wire earth return powerline in one of the fields being sprayed
Source: ATSB
During the fourth run, the pilot completed spraying the first field, including a clean‑up run[4] along the south fence line. They then transited 5 km north and commenced spraying the second field in an east-west racetrack pattern. The pilot applied 2 loads of chemical (runs 5 and 6) to that field. Each run took between 19 minutes and 28 minutes to apply, with the pilot then returning to the supply airstrip for the aircraft to be replenished with chemical and fuel as required.
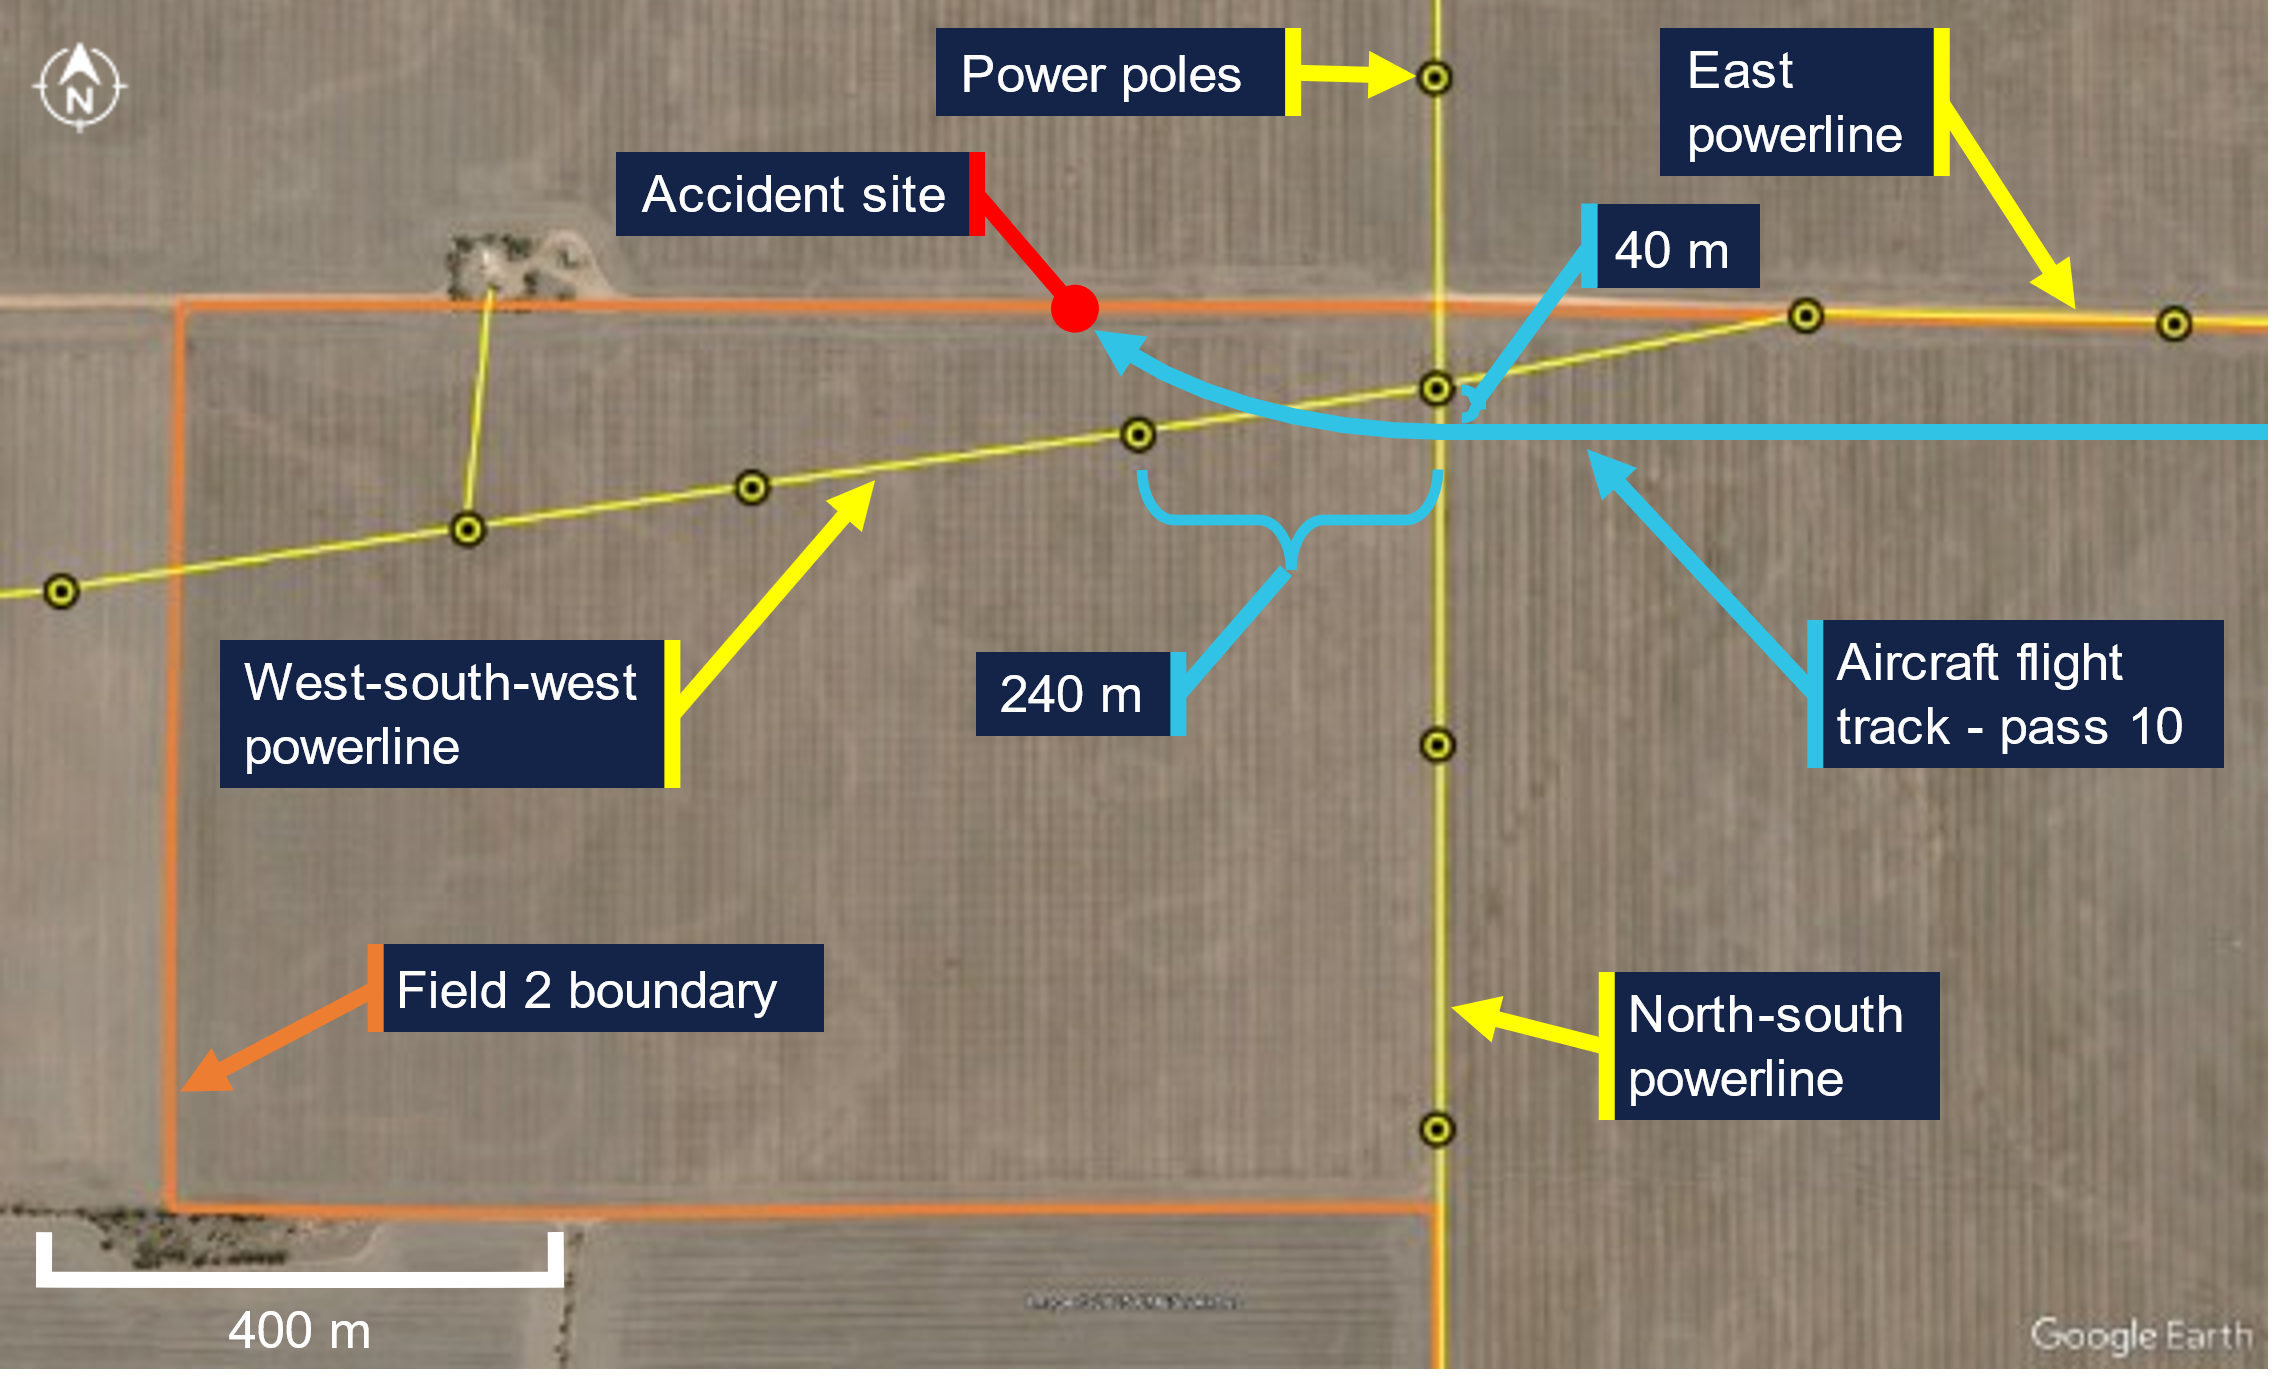
Two 19 kV single‑wire earth return powerlines were positioned in the second field and measured to be around 12 m above the ground. A north‑south powerline bisected the field, and the other powerline ran partially to the east along the northern border (Figure 3 in orange) of the field and partially to the west‑south‑west crossing the north‑west corner of the field. The recorded data showed the pilot mostly flew the aircraft under the north‑south powerline running perpendicular to the spray pass direction, except where the powerline ran adjacent to the edge of the field, where they flew over the powerline.
At about 1307, the pilot departed the supply point and continued spraying the second field. A further 9 passes were completed and approximately 16 minutes into the run, while heading west on pass 10, the pilot flew under the north‑south powerline. At this point, the west‑south‑west powerline crossed the north‑south powerline 40 m to the north (Figure 3). That spray run also aligned with a power pole on the west‑south‑west powerline, 240 m beyond the north‑south powerline. Recorded data showed the aircraft conducted a right turn underneath the second power line after which it collided with terrain at 1323. The aircraft wreckage came to rest on a farm road about 150 m beyond the second power line.
Figure 3: Final pass within field 2 showing the flight path (in blue) and accident site relative to the power lines and poles (the yellow lines and circles respectively)
Source: Google Earth Pro, annotated by the ATSB
The emergency locator transmitter from the aircraft had activated, and the signal was received by the Joint Rescue Coordination Centre which contacted Airservices Australia and the operator. Call logs from the operator indicated that they were notified at 1328 by the coordination centre that the aircraft’s emergency locator transmitter had activated. Personnel from the operator and a local farm worker responded and found the aircraft wreckage at 1338. The pilot was fatally injured and the aircraft was substantially damaged. There was no fire. There were no known witnesses to the accident.
Context
Pilot information
The pilot held a Commercial Pilot (Aeroplane) Licence with a single-engine aeroplane class rating. The pilot had 3,623 hours total aeronautical experience, of which 1,243 hours were conducting agricultural aerial application and 941 hours were on the AT‑802 aircraft type. The pilot also held aerial application (with firefighting endorsement) and low-level ratings. In addition, the pilot held a gas turbine design feature endorsement, and numerous piston and turbine type ratings.
The pilot held a valid class 2 aviation medical certificate with their class 1 medical certificate not being renewed when it expired in November 2023. For the operation being conducted, only a class 2 medical certificate was required.[5] It was reported that the pilot appeared well rested and fully alert for the flight.
Aircraft information
VH-ODX was an Air Tractor Incorporated AT-802A single-seat low-wing tailwheel, fixed landing gear aircraft manufactured in the United States in 2006. It was powered by a Pratt & Whitney Canada PT6A-67AG turboprop engine. It was first registered in Australia in August 2006. The aircraft was configured for aerial spraying, with the spray boom fitted under each wing, aft of the trailing edge, and extending about three-quarters of the wingspan (exemplar shown in Figure 4).
The above image has been modified to remove the registration and other markings. Source: ATSB
The current maintenance release was issued on 30 July 2025. On the day of the accident, the maintenance release indicated the aircraft had 5,595.4 hours recorded as the total time in service.
The aircraft was fuelled from 2 stainless steel transport tanks located on the loader’s truck, which included a single-point filter. A fuel sample, taken from the tanks at Cummins Town aerodrome on 10 September 2025, was observed to be free from water and contaminants.
Meteorological information
The Bureau of Meteorology operated a weather station at Cummins Town aerodrome, 17 km to the south of the accident site, which recorded wind and temperature at 30‑minute intervals. Around the time of the accident, the recorded winds were 11 kt from the west and the temperature was 19°C.
The loader reported the weather at the time of the accident to be clear and sunny with a light westerly breeze.
Wreckage and impact information
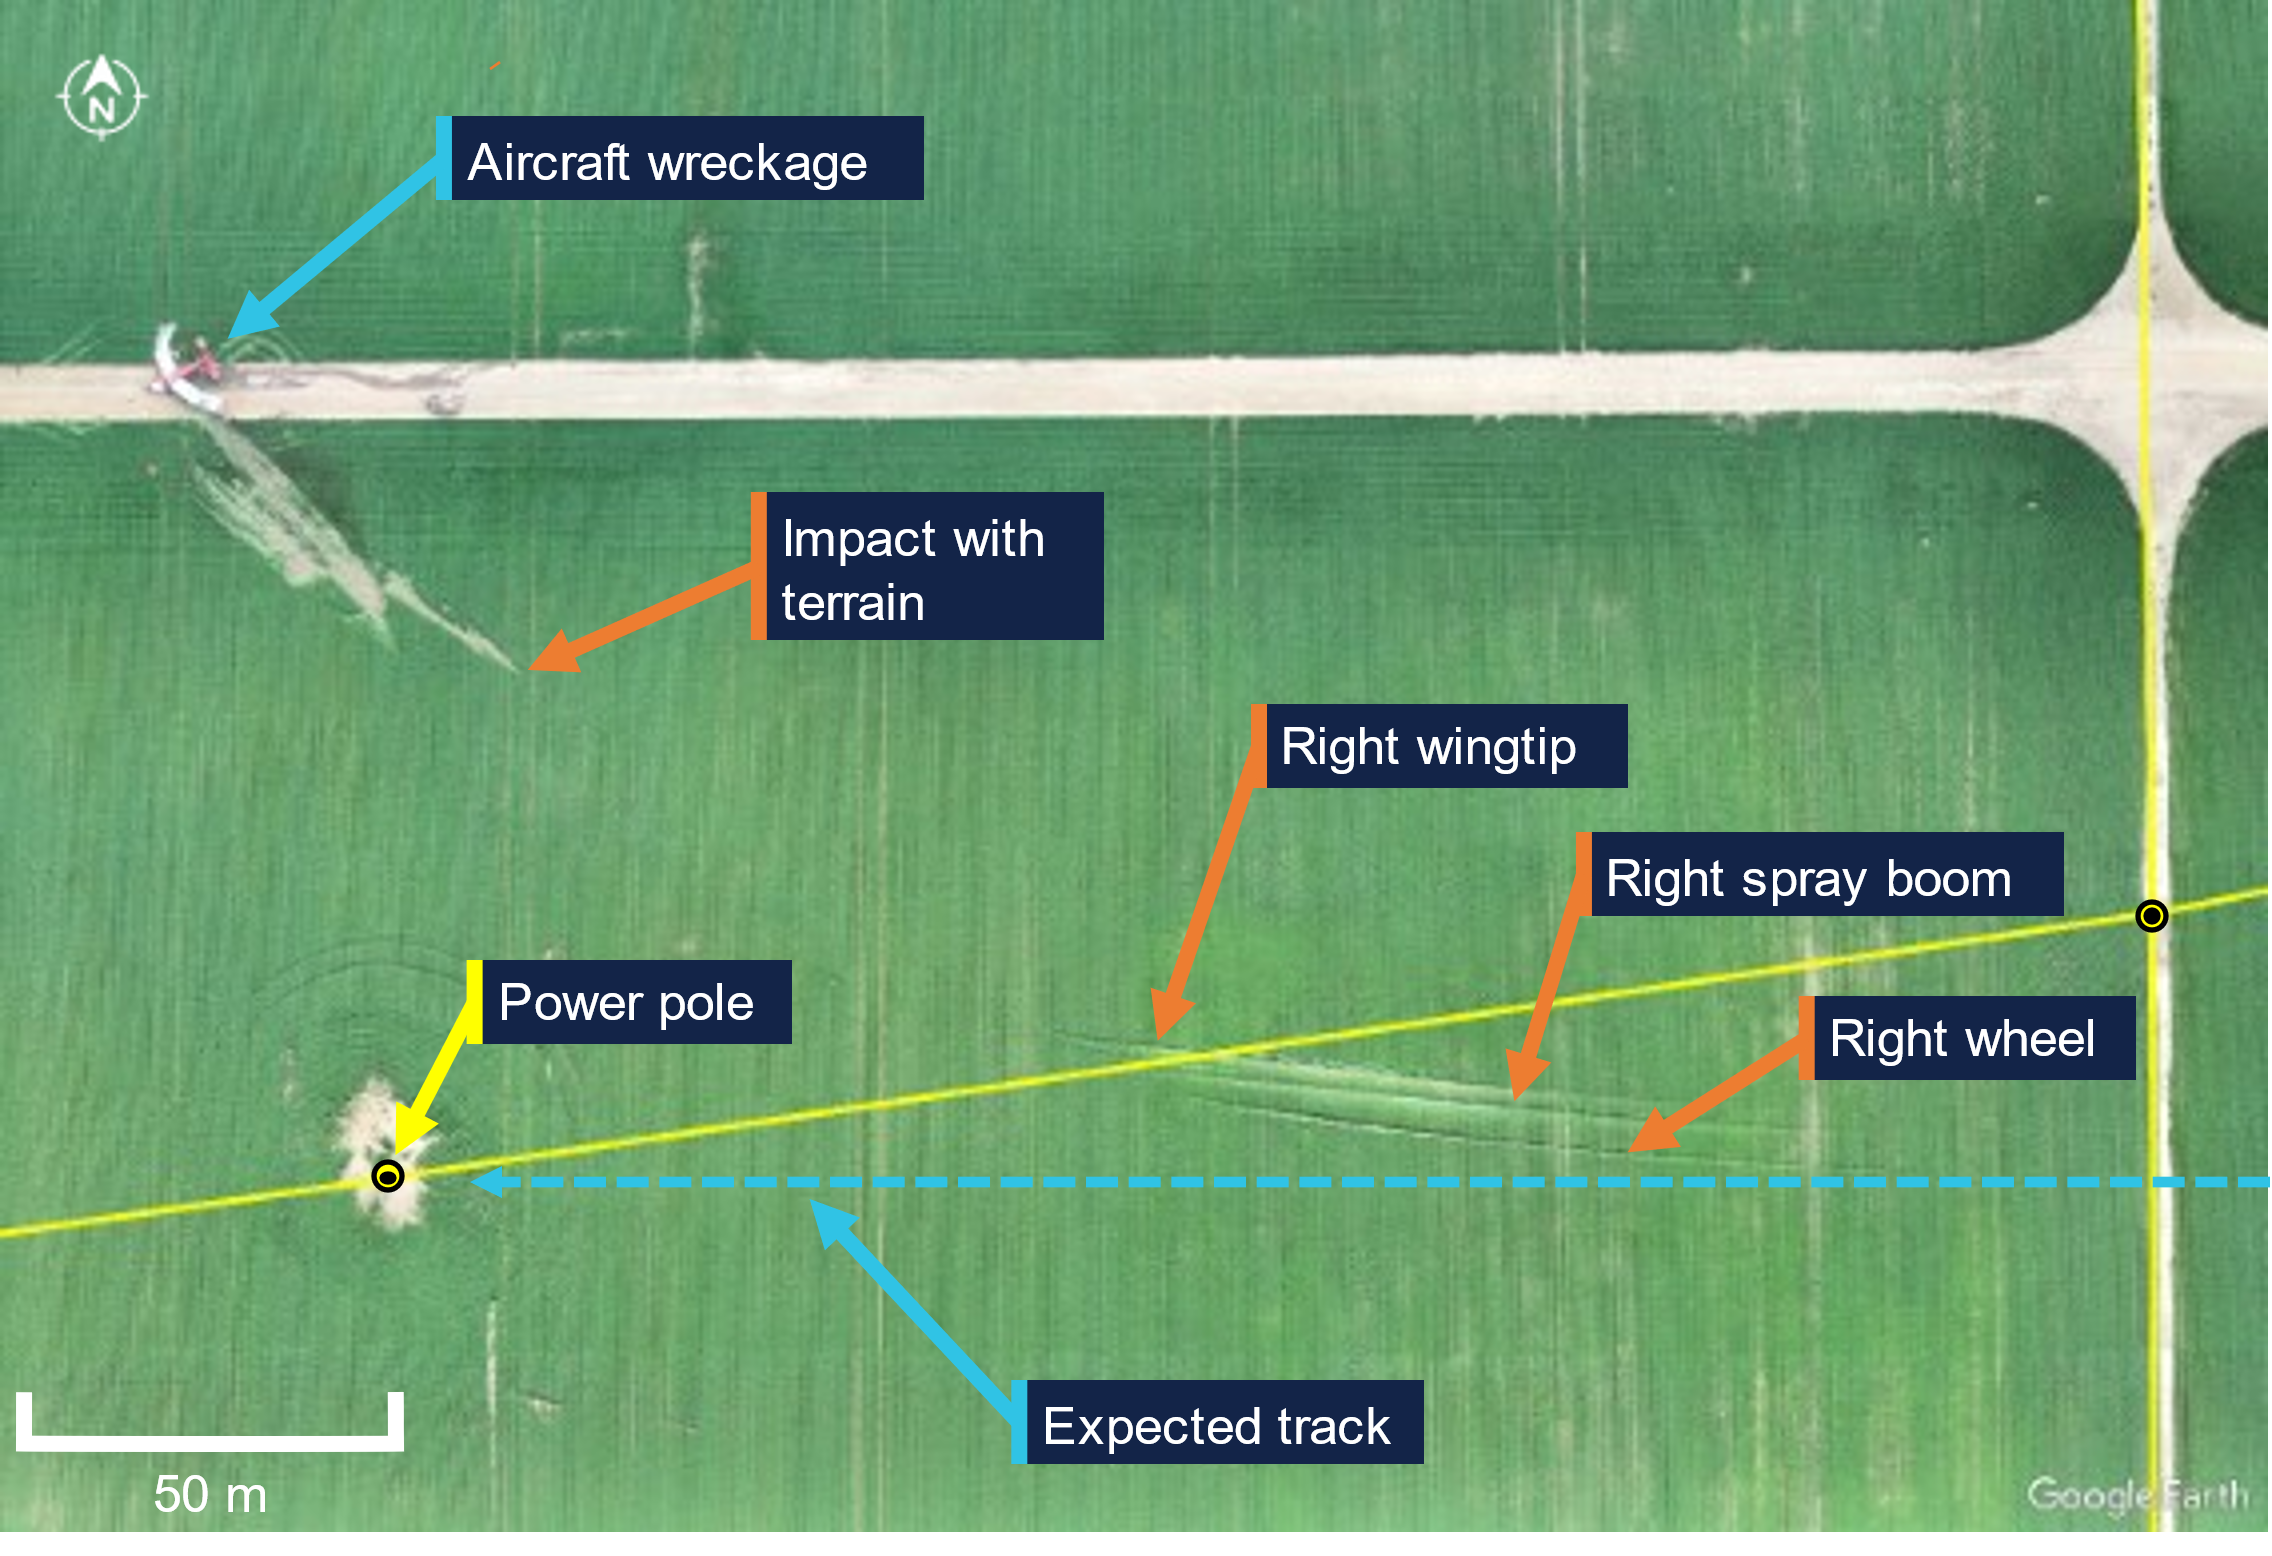
Witness marks matching the right wheel, right spray boom and right wingtip indicated they had passed through the approximately 0.5–1.0 m high wheat crop 260 m prior to the accident site, with the right wheel running along the ground for about 22 m (Figure 5). The crop markings started on a heading of 264° (magnetic) and finished just beyond the west‑south‑west powerline on a heading of 273° after about 125 m. The markings showed that the aircraft was in a significant right skid. Later in the crop markings, the right aileron also left a mark indicating a significant down (left roll) deflection.
Another crop and ground scar from the aircraft had been produced 88 m beyond the initial markings that continued to the wreckage (‘Impact with terrain’ to ‘Aircraft wreckage’ labels in Figure 5). Numerous indicators such as component locations in the debris field, orientation of wheat strands caught in the aircraft structure, and damage signatures to the airframe indicated the aircraft impacted terrain in an inverted orientation, left wing first at a near wings‑level and nose‑down attitude.
Figure 5: Crop witness marks at the accident site
Source: ATSB
All major aircraft components were accounted for at the accident site (Figure 6). There was no evidence of pre‑impact defects with the flight controls or aircraft structure. The propeller assembly separated from the engine during the impact sequence and was located on the farm road, about 18 m behind the front of the fuselage. Two propeller blades had ejected from the propeller hub and one blade had fractured mid‑length. The damage sustained to the propeller assembly was consistent with the engine operating at the time of the ground impact. The wing integral fuel tanks had ruptured during the accident sequence. A residual aroma from spilled fuel was detected at the accident site that persisted for several days.
Figure 6: VH-ODX wreckage
Source: ATSB
Recorded information
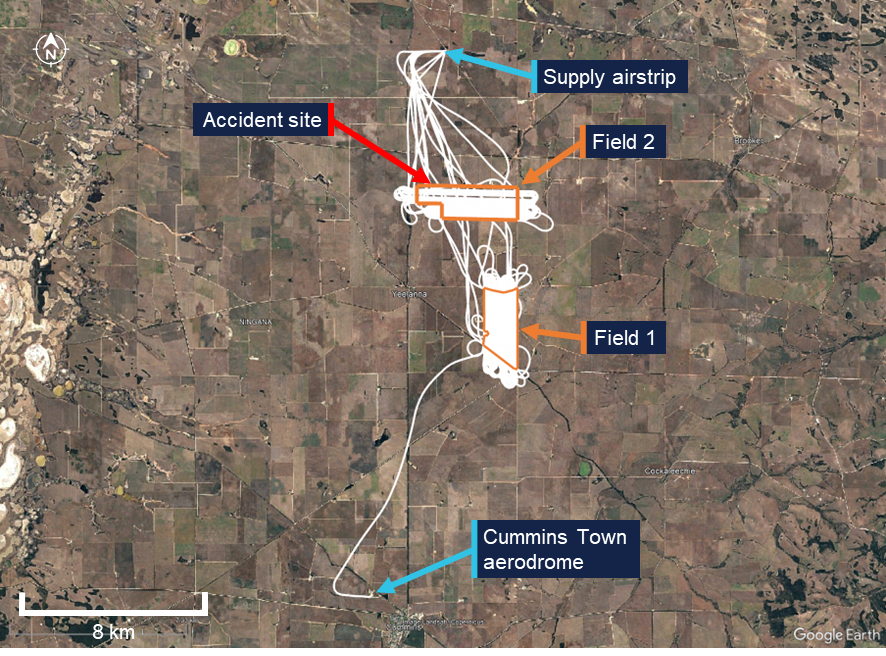
A TracPlus RockAIR portable tracking device had been fitted to the aircraft and was recovered from the accident site. The device was transferred to the ATSB’s technical facilities in Canberra, Australian Capital Territory, where it was interrogated. The recorded data provided the aircraft’s position, altitude, speed and track angle data at 1‑second intervals up until the time of the accident (Figure 7). The data showed the take‑off from Cummins Town aerodrome, the transit to and from the supply airstrip and the completed spray runs in fields 1 and 2. Location and time parameters from the flight data were correlated to identify that the accident occurred at 1323:40.
Figure 7: TracPlus RockAIR broadcast data for VH-ODX on 8 September 2025
Source: TracPlus RockAIR broadcast data on Google Earth Pro, annotated by the ATSB
To assist with aerial application tasks, a Tabula AirVision agricultural application system was fitted to the aircraft. The system had the capability to record parameters such as position and application information. It could also provide live fleet tracking. The unit was recovered from the aircraft and retained by the ATSB for further investigation.
A Perkins Data Acquisition Alarm Monitor was recovered from the aircraft and retained by the ATSB for further investigation. A Replay XD 1080 video camera mount in the cockpit was also recovered. Data extracted from unit contained about 30 GB of good quality video, however, the last recording was from 2016.
Further investigation
To date, the ATSB has examined the site and wreckage, conducted interviews, collected documentation, and recovered recorded data from the accident flight.
The investigation is continuing and will include review and analysis of the:
recorded data
aircraft documentation
operational records
pilot medical records, qualifications and their experience
aerial application standard practices
safety equipment.
A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
Acknowledgements
The ATSB would like to acknowledge the assistance of the South Australia Police during the onsite stages of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
About ATSB reports
ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.
Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau.
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1]The flight was conducted under Part 137 of the Civil Aviation Safety Regulations (aerial application operations).
[2]Loader: the term used to denote ground support personnel whose functions include assisting with mixing chemicals, loading and dispatching the aircraft.
[3]Racetrack pattern: the application pattern that involves making successive overlapping loops across a field.
[4]Pilots delay the commencement of spraying and prematurely shut off spraying at the end of a field to ensure the chemical does not get applied to an adjacent field. A clean‑up run is a spray pass perpendicular to the predominant direction along the edge of a field to ensure crop near that fence line has appropriate coverage.
[5]Civil Aviation Safety Authority exemption EX28/23, in effect at the time of the accident, exempted the pilot from needing to hold a class 1 aviation medical certificate for aerial application flights such as the accident flight. The exemption was subject to the pilot holding a class 2 medical certificate.
Occurrence summary
Investigation number
AO-2025-053
Occurrence date
08/09/2025
Occurrence time and timezone
13:23 Australian Central Standard Time
Location
17 km north of Cummins Town Aerodrome
State
South Australia
Report release date
23/10/2025
Report status
Preliminary
Anticipated completion
Q3 2026
Investigation level
Short
Investigation type
Occurrence Investigation
Investigation phase
Final report: Internal review
Investigation status
Active
Mode of transport
Aviation
Aviation occurrence category
Collision with terrain
Occurrence class
Accident
Highest injury level
Fatal
Aircraft details
Manufacturer
Air Tractor Inc
Model
AT-802A
Registration
VH-ODX
Serial number
802A-0243
Aircraft operator
Aerotech Australasia Pty Ltd
Sector
Turboprop
Operation type
Part 137 Aerial application operations
Activity
General aviation / Recreational-Aerial work-Agricultural spreading / spraying
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 4 August 2025, an amateur-built Lancair IV departed Orange Airport, New South Wales, at 0652 local time, intending to fly to Bankstown Airport.
During cruise, the aircraft sustained an electrical system failure, resulting in numerous electrically driven systems failing. The pilot then made the decision to conduct an air return to Orange Airport, rather than continue the flight towards Bankstown.
Orange Airport consists of primary runway 11/29 which is 2,213 m long and is a sealed surface with a secondary runway 04/22 which is a 964 m long unsealed surface.
Due to the electrical malfunction, several systems of the aircraft were impacted, including the landing gear and VHF radio communication systems. The pilot used their mobile phone to communicate with a ground station to aid in facilitating their arrival at Orange Airport.
As the landing gear system is electrically controlled and hydraulically operated, due to the electrical failure, the primary method of the gear extension was not functional.
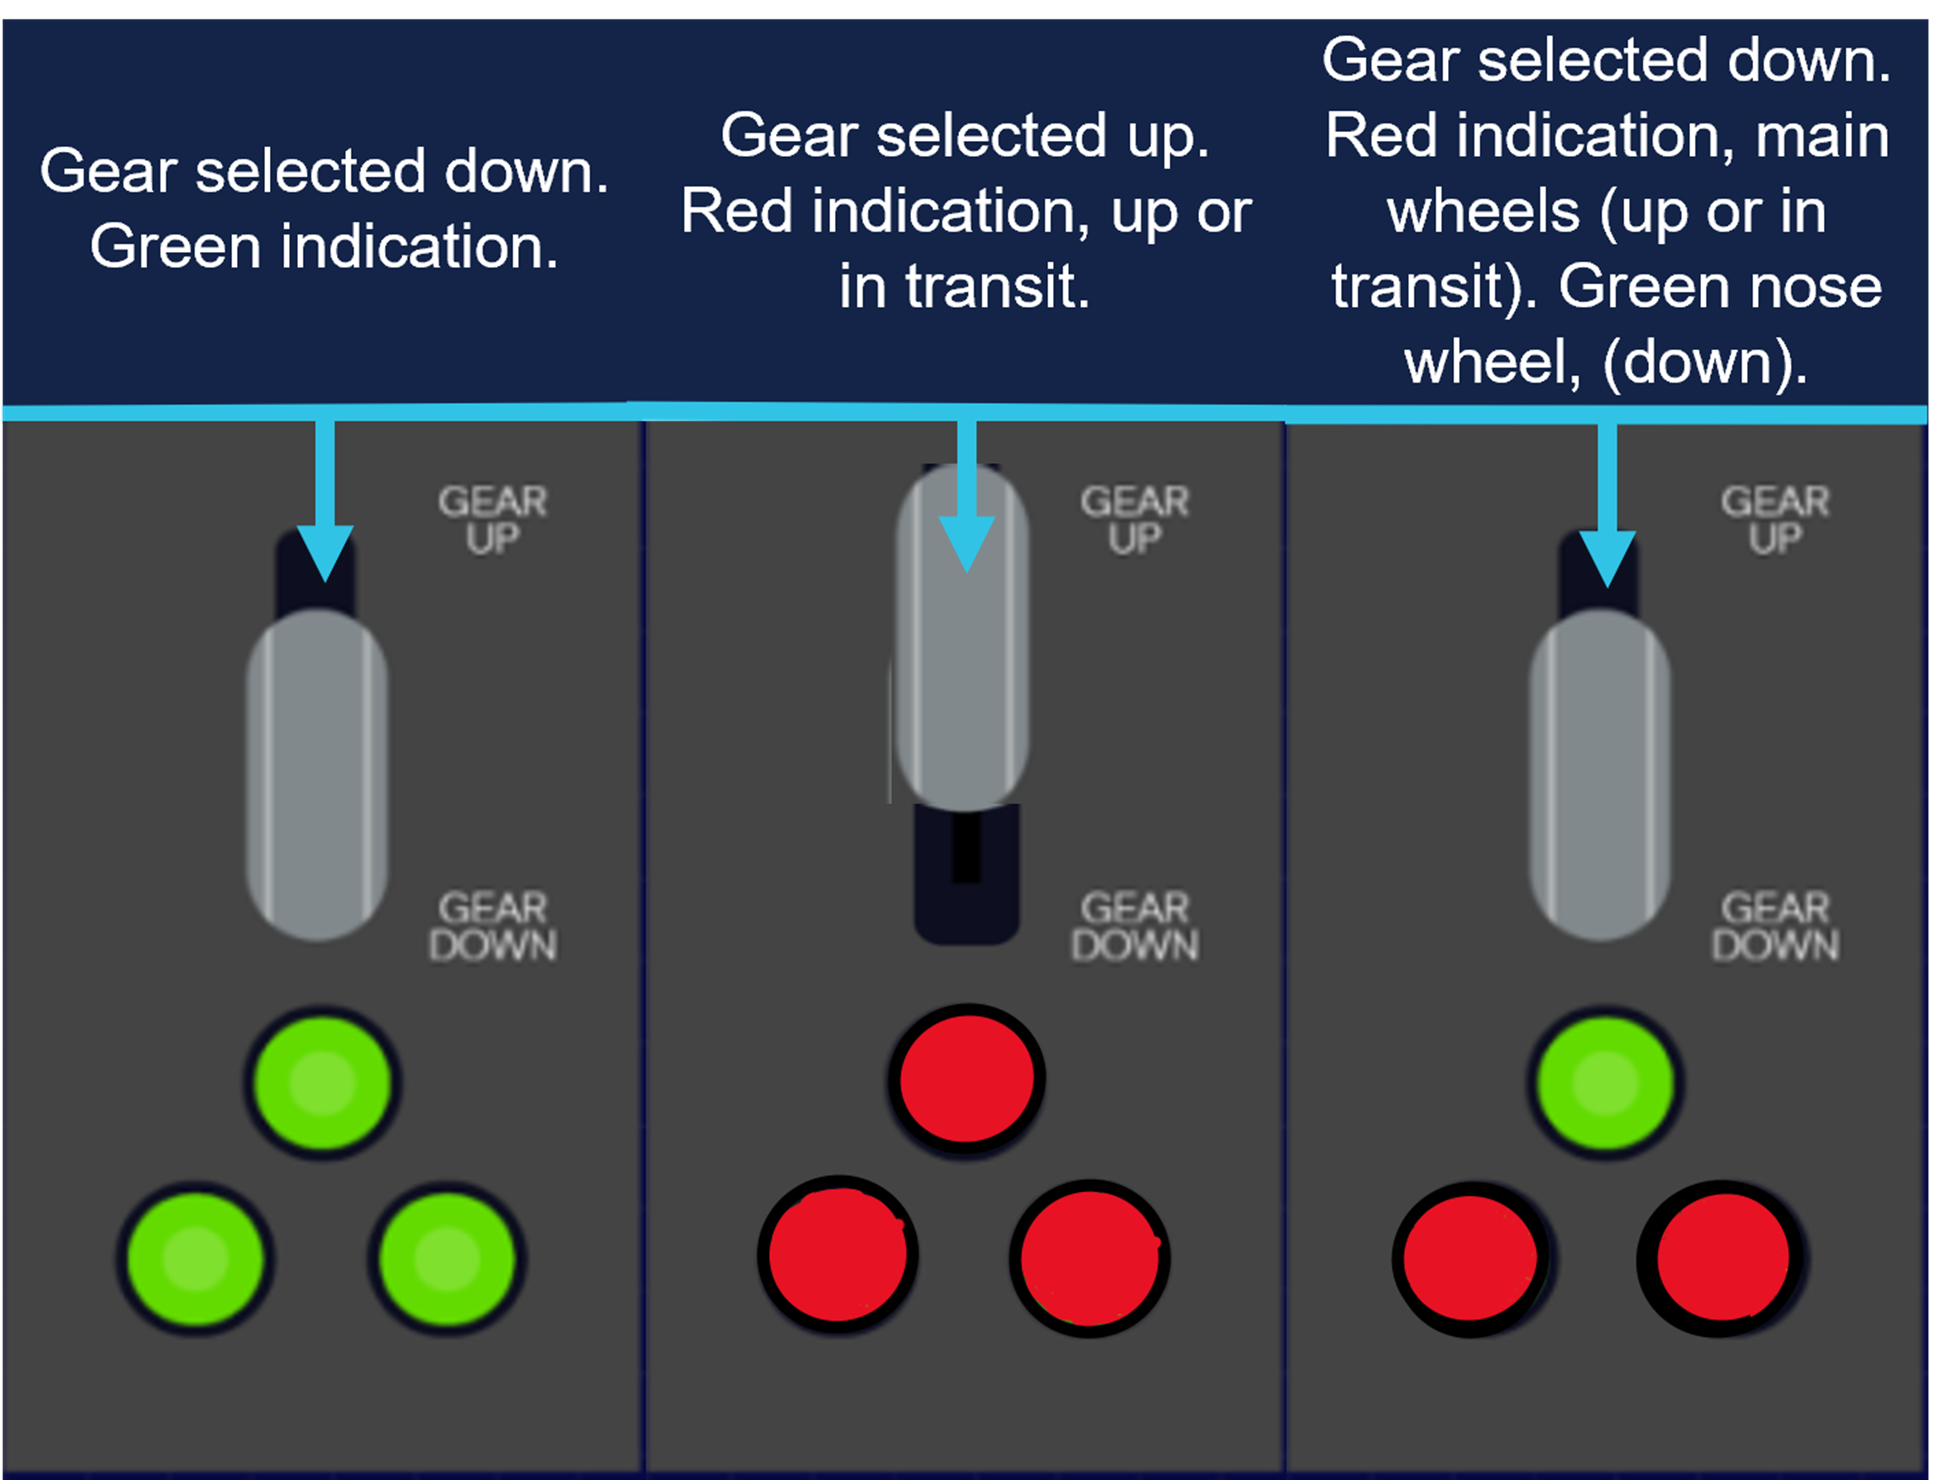
During the initial approach to the primary runway, the pilot manually selected the landing gear ‘down’ to extend the landing gear. Once manually selected ‘down’, the undercarriage extension indicator showed that only the nose gear had locked ‘down’, indicating (green), with the main gear, not indicating that it had ‘locked’ down (Figure 1).
Figure 1: Generic representation of landing gear selection
Source: ATSB representation of landing gear selection and indication. May not be indicative to type of aircraft.
The pilot proceeded to conduct several low passes of the runway to try to ascertain the condition of the landing gear with people on the ground.
However, after not being able to confirm the gear was fully down and locked, the pilot then made the decision to conduct a precautionary landing on the non-sealed cross strip, runway 04.
The pilot conducted the approach and landed, however on touchdown the main undercarriage legs collapsed, and the aircraft slid on the nosewheel (front of the aircraft) and rudder (rear of the aircraft) before coming to rest at the fence at the end of the runway.
The aircraft incurred some minor damage (Figure 2) to the wingtip and elevator with no injuries to the pilot.
Figure 2: Damage to aircraft
Source: Operator, annotated by the ATSB
Subsequent engineering inspections found the electrical system had failed due to a defective voltage regulator.
Safety message
This occurrence illustrates that a good knowledge of aircraft systems coupled with sound decision‑making can help facilitate a positive outcome to an emergency.
Aircraft rely on hydraulic or electrical systems to extend and retract the landing gear. Should any component in these systems fail, pilots may be left with no choice but to manually extend the undercarriage or potentially execute a wheels-up landing.
Applying a structured and proactive approach to identifying and managing threats and errors, influences the safety of the flight.
In this instance, the pilot was able to identify the aircraft system failure and make several calculated risk-based decisions to manage the emergency. This was achieved by using various resources at their disposal, such as their mobile phone, to seek ground assistance in the absence of normal VHF radio.
In emergency situations, pilots need to utilise all the available resources at their disposal. Maintaining a degree of flexibility and adapting to select the most appropriate landing area can minimise risk, limit damage and maximise survivability.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence summary
Mode of transport
Aviation
Occurrence ID
AB-2025-039
Occurrence date
04/08/2025
Location
Orange Airport
State
New South Wales
Aviation occurrence category
Collision with terrain, Diversion/return, Electrical system, Landing gear/indication, Runway excursion, Wheels up landing
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 30 July 2025, at 0741 local time, an Australian-registered amphibious Air Tractor AT‑802, configured for firefighting and with 2 crew members on board, departed from Thessaloniki Airport Makedonia, Greece. The aircraft, along with 2 other company aircraft, was headed to a fire located about 40 km north of the airport. At about 20 km south of the fire location, all 3 aircraft commenced water scooping operations at Lake Koroneia.
The amphibious aircraft was designed to scoop water by lowering a retractable intake hole underneath the aircraft while skimming the surface of a body of water at high speed, using the forward motion to force water into the onboard tanks. Prior to scooping operations, pilots will conduct a visual inspection of the proposed scooping area to look for obstacles both on top of and submerged in the water.
The pilot conducted a water inspection and recalled that the water appeared murky and was difficult to see through. During water uplift, the crew of the aircraft reported hearing an impact and immediately initiated a climb to gain height.
The 2 accompanying aircraft flew alongside the Air Tractor to conduct a visual inspection and reported that the right float had dislodged from its mounts. All 3 aircraft made the decision to return to Thessaloniki Airport, with the pilot of the Air Tractor notifying air traffic control and declaring an emergency.
At 0817 the Air Tractor landed on runway 34, however the damaged right float struts were unable to support the weight of the aircraft, and it collapsed onto the right float after landing (Figure 1). The aircraft was subsequently stranded on the runway and emergency services attended. The crew members evacuated the aircraft without injury.
Following the accident, the pilot reported that all 3 aircraft had successfully completed water uplifts from the same location on the previous day. On this occasion, the pilot reported that the glassy water conditions[1] made it difficult to establish the aircraft's height above the water's surface, and the aircraft had hit a submerged object during the scooping run. Due to the risk of unknown hazards at this location, the operator sent a direction to all crew to suspend scooping operations from Lake Koroneia until further notice.
Figure 1: Damaged float struts led to collapse on landing
Source: Operator
Safety message
In murky water, obstructions may not always be visible and the potential for hitting submerged or partly submerged debris is an ever‑present hazard for such operations. Overflying the intended scooping area to scan for such obstacles is always good practice.
In this case, the crew’s quick actions to discontinue operations and pre‑organise emergency services at the airport for their arrival, decreased the risk of injury during their emergency landing.
The hazards that exist in conducting low‑level operations over water have long been recognised (ATSB, 2012) and include the risks of visual illusion and altered depth perception. These factors can make it difficult for pilots to accurately judge the height above water, especially over featureless or reflective surfaces. Flying over calm, glassy water is particularly dangerous, but even choppy water with a constantly varying surface interferes with normal depth perception. Regularly checking the altimeter and establishing smooth descent rates for water alighting during such operations can assist in raising safety margins.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report and allow for greater industry awareness of potential safety issues and possible safety actions.
[1]Glassy water can be present across a broad spectrum, from a mirror-like surface to rippled or wavy water, which reflects a distorted image. The reason it presents a challenge for pilots is that without texture on the surface of the water, it is more difficult to judge height.
Occurrence summary
Mode of transport
Aviation
Occurrence ID
AB-2025-036
Occurrence date
30/07/2025
Location
20 km north-north-east of Thessaloniki Airport Makedonia
State
International
Aviation occurrence category
Collision with terrain, Diversion/return, Ground strike, Landing gear/indication
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 28 June 2025, a Bell Helicopter 47G-5 was conducting a ferry flight from Clare Valley Aerodrome, South Australia to Sydney, New South Wales. The pilot and passenger departed Clare Valley at about 0900 local time for an intended fuel stop at Renmark Airport, South Australia.
At about 0950, while in cruise flight at about 800 ft above ground level, the pilot felt a ‘couple of small kicks’ (in yaw[1]) and a ‘small shake’ alerting them to a problem. The pilot started to reduce power and altitude and scan the instruments and recalled that the carburettor[2] air temperature indicated the highest temperature on the gauge, although no carburettor heat was being applied. The engine then subsequently failed and the pilot conducted an autorotation[3] into a nearby field.
A run-on landing was conducted with forward speed, before the starboard side skid gear collapsed, causing the cabin to dig into the dirt whereby the helicopter tipped nose forward. As a result, the windscreen bubble ruptured, the advancing blade then struck the ground and severed the tail boom, with the helicopter coming to rest in an upright position, but substantially damaged (Figure 1).
Figure 1: Helicopter damage
Source: Operator
The pilot reported securing the cabin, switching the magnetos[4] and battery off and shutting off fuel (closing the fuel cut-off value). On exiting, the starter motor was smoking, the starter vibrator was buzzing, and the battery relay was chattering. The pilot then disconnected the battery which de-energised the starter system.
No injuries were reported by pilot or passenger.
Engineering inspection
Prior to the aircraft being recovered, engineers confirmed that the battery relay was energising, and the starter vibrator was also receiving power with the master switch in the OFF position when the battery was connected.
A subsequent engineering assessment detected heat damage in the main canon plug connector (connecting the cabin wiring loom with the airframe wiring loom) under the cabin floor, and heat damage in the wiring.
The assessment determined that corrosion in the plug wiring pins (Figure 2) has likely caused resistance to electrical current, and heat build-up. This likely resulted in several wires melting and creating a short circuit for the battery relay, starter vibrator, and instrument cluster.
The operator reported that the short circuit energised the starter vibrator and provided grounding to the magnetos which affected engine operation.
Figure 2: Corrosion in the plug wiring pins
Source: Iconic Helicopters Maintenance Pty Ltd
Safety message
Precise positioning and energy maintenance is required for a successful autorotation landing. Autorotation is a high-risk skill requiring the pilot to descend the helicopter by lowering the collective lever so that the resultant airflow provides the driving force to turn the blades. Thorough and regular training in emergency procedures is crucial for all pilots.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
[1]The motion of an aircraft about its vertical or normal axis.
[2]Device for continuously supplying the engine with optimum combustible mixture.
[3]Autorotation is a condition of descending flight where, following engine failure or deliberate disengagement, the rotor blades are driven solely by aerodynamic forces resulting from rate of descent airflow through the rotor. The rate of descent is determined mainly by airspeed.
[4]A type of electric generator using permanent magnets to supply an electric current for engine ignition.
Occurrence summary
Mode of transport
Aviation
Occurrence ID
AB-2025-027
Occurrence date
28/06/2025
Location
51 km from Waikerie
State
South Australia
Occurrence class
Accident
Aviation occurrence category
Abnormal engine indications, Collision with terrain, Engine failure or malfunction, Forced/precautionary landing
Highest injury level
None
Brief release date
08/08/2025
Aircraft details
Manufacturer
Bell Helicopter Co
Model
47G-5
Sector
Helicopter
Operation type
Part 91 General operating and flight rules
Departure point
Clare Valley Aircraft Landing Area, South Australia
On 13 September 2024, a BRM Aero Bristell Classic, registered 23-2136, collided with terrain about 32 km south of Bendigo aerodrome, Victoria. The pilot was fatally injured and the aircraft was destroyed by post-impact fire.
As part of an investigation by the Coroners Court of Victoria, Victoria Police requested assistance from the ATSB in the examination of components from the aircraft. The ATSB commenced an investigation under the Australian Transport Safety Investigation Act 2003.
The ATSB has completed its work recovering the recorded flight path data from the supplied avionics. A copy of the data and a report detailing the work undertaken by the ATSB was provided to Victoria Police on 17 March 2026.
Any enquiries relating to the investigation should be directed to Victoria Police.
Last updated:
Occurrence summary
Investigation number
AE-2024-007
Occurrence date
13/09/2024
Location
32 km south of Bendigo Airport
State
Victoria
Investigation type
External Investigation
Investigation status
Completed
Mode of transport
Aviation
Aviation occurrence category
Collision with terrain
Occurrence class
Accident
Highest injury level
Fatal
Aircraft details
Manufacturer
BRM Aero S.R.O.
Model
Bristell Classic
Registration
23-2136
Sector
Piston
Operation type
Part 103 Sport and recreational aircraft
Activity
General aviation / Recreational-Sport and pleasure flying-Pleasure and personal transport