Fairchild SA227-AC, VH-SEF, Brisbane Airport, 9 October 2003

Summary

Preliminary investigation was undertaken into a category 4 occurrence involving a Metroliner aircraft and a Bell 47 helicopter at Brisbane Airport. The ATSB has terminated the investigation based on information from Airservices Australia, following that organisation's investigation into the circumstances of the occurrence.

Status: Downgraded the occurrence to category 5 and investigation discontinued.

Occurrence summary

Investigation number 200304220
Occurrence date 09/10/2003
Location Brisbane airport
Report release date 09/10/2003
Report status Discontinued
Investigation status Discontinued
Mode of transport Aviation
Aviation occurrence category Loss of separation
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Fairchild Industries Inc
Model SA227
Registration VH-SEF
Serial number AC-641
Operation type Air Transport Low Capacity
Damage Nil

Aircraft details

Manufacturer Bell Helicopter Co
Model 47
Registration VH-SON
Serial number 3135
Sector Helicopter
Operation type Aerial Work
Damage Nil

British Aerospace Plc BAe 146-100, VH-NJV, Sydney Airport, NSW, 22 September 2003

Summary

Preliminary investigation was undertaken into a category 4 occurrence involving a BAE 146 aircraft and a tug vehicle towing an aircraft at Sydney Airport. The ATSB has terminated the investigation based on evidence gathered that identified a misunderstanding had occurred due to poor communication. There was no safety benefit to be gained from continuing the investigation.

Status: Downgraded the occurrence to category 5 and investigation discontinued.

Occurrence summary

Investigation number 200304119
Occurrence date 22/09/2003
Location Sydney, Airport
Report release date 22/09/2003
Report status Discontinued
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Aviation
Aviation occurrence category Runway incursion
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer British Aerospace
Model BAe 146
Registration VH-NJV
Operation type Air Transport High Capacity
Damage Nil

Bell 206B, VH-EWH

Summary

The Bell 206 helicopter was being operated on water-bombing tasks in support of fire-fighting east of Armidale, NSW. As the pilot commenced a climb following water pick-up, the `engine out’ audio warning sounded, and the master warning annunciator illuminated as the engine failed. The pilot jettisoned the water and Bambi bucket and conducted an autorotative descent into a cleared area. During the landing the helicopter's main rotor contacted the tail boom and severed the tail rotor assembly. The pilot, the sole occupant, was not injured. The pilot indicated that immediately following the accident, he drained approximately 0.5L of fuel from the helicopter to check for water contamination and fuel boost pump operation.

Occurrence summary

Investigation number 200304105
Occurrence date 01/10/2003
Location 40 km E Armidale, (NDB)
State New South Wales
Report release date 12/07/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Fuel starvation
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Bell Helicopter Co
Model 206
Registration VH-EWH
Serial number 1380
Sector Helicopter
Operation type Aerial Work
Departure point East of Armidale, NSW
Destination East of Armidale, NSW
Damage Substantial

Piper PA-23-250, VH-WAC

Summary

The pilot, his wife and three children were conducting a private flight from Mareeba, Queensland to Roma, Queensland in the Piper PA-23-250 Aztec aircraft, registered VH-WAC. Prior to departure, the pilot was observed conducting pre-flight activities, including an aircraft inspection, refuelling the aircraft, and engine run-ups.

Related Documents: | Media Release |

Occurrence summary

Investigation number 200304091
Occurrence date 01/10/2003
Location 1 km WSW Mareeba, Aero.
State Queensland
Report release date 13/01/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Piper Aircraft Corp
Model PA-23
Registration VH-WAC
Sector Piston
Operation type Private
Departure point Mareeba, QLD
Destination Roma, QLD
Damage Destroyed

Robinson R22, VH-UXF, on 28 September 2003

Summary

On 28 September 2003, a Robinson Helicopter Company model 22 helicopter (R22) registered VH-UXF was engaged in aerial mustering operations with another R22 helicopter registered VH-AOP. The helicopters were operating in an area 93 km south of Derby, Western Australia. The pilot of UXF returned from a refuelling stop and had been in the mustering area for about 30 minutes when the pilot of AOP noted that he had not heard any radio transmissions from the pilot for about 10 minutes. He commenced a search and soon after, located UXF at the edge of a claypan.

The pilot landed close to UXF in order to assist the two occupants. After isolating the helicopter's electrical system, he attempted to comfort and provide first aid to them. However, because of the apparent nature and extent of their injuries, he decided to seek medical assistance from Derby.

About 80 minutes later, the pilot returned to the scene of the accident with a doctor from Derby. The doctor determined that, in the intervening period, both occupants of UXF had succumbed to their injuries.

WA Coroner

ATSB response to WA Coroner

On 29 September 2010, the Western Australia Deputy State Coroner, Ms Evelyn Vicker, handed down her findings in the inquest into two deaths arising from a Robinson R22 helicopter accident that occurred on 28 September 2003 near Derby in Western Australia.  The ATSB had previously investigated this accident and published its finding on the ATSB website: ATSB investigation 200304074.  The Coroner fully agreed with the ATSB's findings.

The ATSB's key findings in the helicopter accident were:
1.    The failure of the A166 clutch shaft, involving torsional fatigue cracking, which was due to the inappropriate assembly of the shaft to the A907 yoke.
a.    a non approved jointing compound was used during the assembly; and
b.    the bearing blocks were installed over the painted yoke surface

2.    A loss of main rotor drive which was most likely to have occurred at a combination of height and speed that was insufficient to enable the pilot to conduct a successful auto rotation.

Two recommendations from the Coroner affect the ATSB:

Recommendation 3

CASA [Civil Aviation Safety Authority] seek input from the ATSB as to the reasonableness of mandatory inspection of both yoke and clutch shaft attachments in helicopters operating at low height for evidence of fretting in view of the fact this seems to have been a factor in failure of the A166 component in an R22 in 1992, 2003 and 2005.

ATSB Response:

The ATSB wishes to draw attention to the safety actions on page 10 of the ATSB's accident investigation report.  As a result of an ATSB recommendation on 6 November 2003, CASA issued Airworthiness Directive AD/R22/51 which mandated inspections of the A166 shaft to A907 yoke on all R22 helicopters operating in Australia.

CASA also issued AD/R44/019 on 28 November 2003, mandating the same inspection on those R44 helicopters that had the C166 shaft to C907 yoke disassembled since installation at the factory.

On 7 May 2009 the Airworthiness Directives were cancelled by CASA because the instructions contained in them with respect to mandatory inspections were introduced by Robinson Helicopters into the maintenance manuals for the R22 and R44 models.

The ATSB has been advised by CASA:

"In light of the fact that the relevant maintenance manuals were updated to adequately reflect the maintenance practices required by the ADs, it was considered that the ADs were no longer required and they were subsequently withdrawn.

The ADs were no longer considered necessary because person's performing maintenance on Australian Aircraft are required to do so in accordance with the instructions contained in the applicable approved maintenance data (which includes the manufacturer's maintenance manual) - see r.42V of the Civil Aviation Regulations 1988."

The review of the maintenance manuals for the R22 and R44 helicopters in light of this accident and the findings of the ATSB led CASA to the conclusion that there was a heightened risk of improper maintenance practices being employed in the assembly of the clutch shafts in these types of helicopter. CASA addressed this risk by promulgating the ADs which were later adopted by the Robinson Helicopter Company. CASA considers that this risk is now adequately addressed via the amendments which have now been made to the manufacturer's maintenance manuals for both helicopter types."

The ATSB notes that it is normally CASA that would make an assessment as to the reasonableness of the implementation of a specific recommendation after a safety issue has been identified.  In this instance the ATSB issued the initial recommendation on 6 November 2003.  The ATSB is satisfied with CASA's response that the inspection requirement to address improper maintenance practices is contained in the Robinson Maintenance Manuals and mandated through the application of regulation 42V of the Civil Aviation Regulations 1988.

Recommendation 5

ATSB continue to circulate relevant investigation findings to the industry to remind operators and maintenance engineers manufactures recommendations are made for sound technical reasons.

ATSB Response:

The ATSB wishes to draw attention to section 12AA of the Transport Safety Investigation Act 2003 (TSI Act) which outlines that the ATSB's function is to improve transport safety through means that include:
-    Identifying factors that have contributed to transport safety matters;
-    Identifying factors that might affect transport safety;
-    Communicating those factors to relevant sectors of the transport industry and the public.

Through its investigation and research and analysis activities the ATSB is committed to fostering safety awareness, knowledge and action.  During the course of an ATSB investigation or research project the ATSB works with the relevant sectors of the industry to encourage safety action as safety issues are identified.  The final report is always published on the ATSB's website and hard copies made available as required.  Further, the ATSB regularly issues media releases and alerts to provide notification of the Bureau's activities.

Education materials are also supported and issued by the ATSB.

Cooperation with Coroners

ATSB investigations are conducted with the objective of providing findings that can be used to improve transport safety in the future.  Coronial Inquests are a separate process to the ATSB investigation and they are usually supported by their own investigation and brief of evidence.  However, as Inquests also have the objective of seeking to prevent a death occurring again, the ATSB provides cooperation through the explanation of the ATSB's findings in its report.  The ATSB appreciates the interest of Coroners in working with the ATSB in the interests of improving future safety.

Questions concerning the inquest findings should be directed to the Coroner's Court in Western Australia:
Western Australian Coroner's Court
Level 10
Central Law Courts
501 Hay Street
PERTH WA 6000


Occurrence summary

Investigation number 200304074
Occurrence date 28/09/2003
Location 93 km S Derby
State Western Australia
Report release date 13/10/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Transmission and gearbox
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22
Registration VH-UXF
Serial number 0065
Sector Helicopter
Operation type Aerial Work
Departure point Yakka Munga Station
Destination Yakka Munga Station
Damage Substantial

Avionics smoke warning

Summary

Discontinued Investigation

Statement of Reasons

Occurrence investigations commenced from 1 July 2003 are initially categorised as category 4 unless agreed by the ATSB Executive to be above this level at the outset. As detailed in Section 21 (2) of the TSI Act 2003, the Executive Director in empowered to discontinue an investigation at any time. Section 21 (3) of the TSI Act 2003 requires the Executive Director to publish a statement setting out the reasons for discontinuing an investigation (commenced from 1 July 2003) within 28 days of discontinuing the investigation. To obtain a copy of the Brief Print Public for Discontinued Investigations prior to 1 July 2003.


Preliminary investigation was undertaken into a category 4 occurrence where the incident featured an avionics smoke warning. There was no evidence of smoke reported by the flight or cabin crew. Subsequent inspection by maintenance personnel showed no evidence of smoke. The reason for the spurious warning was attributed to dust-disturbance that may have activated the smoke sensor.

Status: Downgraded the occurrence and investigation discontinued.

Occurrence summary

Investigation number 200303985
Occurrence date 09/10/2003
Location Unknown
Report release date 09/10/2003
Report status Discontinued
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Aviation
Aviation occurrence category Warning devices
Occurrence class Incident
Highest injury level None

Avionics smoke warning

Summary

Discontinued Investigation

Statement of Reasons

Occurrence investigations commenced from 1 July 2003 are initially categorised as category 4 unless agreed by the ATSB Executive to be above this level at the outset. As detailed in Section 21 (2) of the TSI Act 2003, the Executive Director in empowered to discontinue an investigation at any time. Section 21 (3) of the TSI Act 2003 requires the Executive Director to publish a statement setting out the reasons for discontinuing an investigation (commenced from 1 July 2003) within 28 days of discontinuing the investigation. To obtain a copy of the Brief Print Public for Discontinued Investigations prior to 1 July 2003.


Preliminary investigation was undertaken into a category 4 occurrence where the incident featured an avionics smoke warning. There was no evidence of smoke reported by the flight or cabin crew. Subsequent inspection by maintenance personnel showed no evidence of smoke. The reason for the spurious warning was attributed to dust-disturbance that may have activated the smoke sensor.

Status: Downgraded the occurrence and investigation discontinued.

Occurrence summary

Investigation number 200303987
Occurrence date 09/10/2003
Location Unknown
Report release date 10/10/2003
Report status Discontinued
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Aviation
Occurrence class Incident
Highest injury level None

Piper Aircraft Corporation PA31-350, VH-TAS

Summary

The ATSB commenced an investigation into the circumstances surrounding an accident involving a Piper Aircraft Corporation PA31-350 aircraft, registered VH-TAS, at Canberra Airport, ACT, on 12 Sep 2003, in which the aircraft landed on runway 30 with the landing gear in the retracted position. After attending the accident site and assessing initial information, a decision was made that there would be limited safety benefit in continuing the investigation.

Occurrence summary

Investigation number 200303924
Occurrence date 21/09/2003
Location Canberra Airport
Report release date 21/10/2003
Report status Discontinued
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Aviation
Aviation occurrence category Wheels up landing
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Piper Aircraft Corp
Model PA-31
Registration VH-TAS
Operation type Air Transport Low Capacity
Departure point Williamtown, NSW
Destination Canberra, ACT
Damage Substantial

de Havilland Canada DHC-8-102, VH-TNG

Appendices

Appendix A.

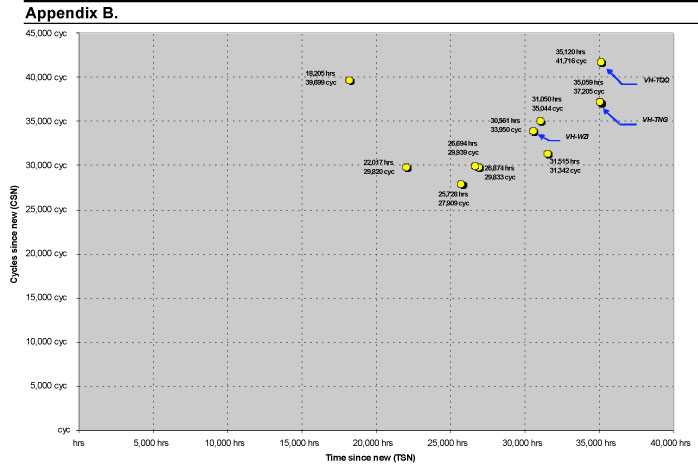
Failure DateModel DHC-8Aircraft SNAircraft TTISAircraft TCISActuator
PN A44700-
Actuator SNActuator TSNActuator CSNFailure ModeActuator PositionHydraulic System
2000079922,668 hrs         
2000098925,019 hrs         
2000186015,217 hrs         
4/02/200010224745009BurstLeft Outboard2     
27/10/200000722,017 hrs29,820 cycCracked       
05/20021690          
23/07/20021023082687429833009114826,874 hrs29,833 cycCrackedRight Inboard1
2/08/20021022892669429939009115426,694 hrs29,939 cycCrackedRight Inboard1
01/20030837          
02/2003090631,050 hrs35,044 cyc        
18/05/2003[2]10214009096330,561 hrs33,950 cycCrackedLeft Outboard2  
6/09/2003[1]41009016335,059 hrs37,205 cycBurstLeft Outboard2   
07/2003167318,205 hrs39,699 cyc        
08/2003176425,728 hrs27,909 cyc        
23/10/200310200931,515 hrs31,342 cycCrackedLeft Outboard2    
7/9/2004[3]102204009095435,120 hrs41,716 cycBurstRight Outboard2  

Notes:
SN - serial number
PN - part number
TTIS - total time in service
TCIS - total flight cycles in service
TSN - time since new
CSN - flight cycles since new
[1] - VH-TNG, subject occurrence
[2] - VH-WZI occurrence
[3] - VH-TQQ occurrence
Absence of information indicates data not available for the relevant occurrence.

aair200303861_002.jpg

Findings and Safety Action

FINDINGS

The investigation identified the following contributing safety factors.

  • The part number A44700-009 roll spoiler actuator, as fitted to TNG, was susceptible to fatigue cracking as a result of deficiencies within the design of the actuator cylinder base
  • The actuator ruptured as a result of fatigue cracking initiated due to the design deficiency and the accumulation of a sufficient number of flight cycles
  • Rupture of the actuator allowed the loss of fluid contents from the number 2 hydraulic system, and the subsequent failure of that system.

SAFETY ACTION

Aircraft manufacturer

On 18 August 2004, the manufacturer issued In-Service Activity Report (ISAR) 2004-07-2760 advising that it considered the overall risks associated with the failure of the actuator as low, and to raise operator awareness of the actuator failure mechanism.

Transport Canada

Transport Canada, being the certification authority for the Dash 8 series of aircraft, conducted its own investigation of the issues associated with actuator failure. In communication with the ATSB, Transport Canada concurred with the aircraft manufacturer's risk management position and agreed that on the basis of current failure rates, no additional action was warranted.

Australian Transport Safety Bureau

The ATSB reviewed the responses and positions of the aircraft manufacturer, Transport Canada and the aircraft operator in relation to the potential for roll spoiler actuator failure to affect operational safety of the Dash 8. While it supports the risk management approach adopted by the manufacturer and Transport Canada, the ATSB believes that the issue of landing performance limitations imposed by a hydraulic system failure is not adequately addressed by this approach. Therefore, the ATSB issues the following safety advisory notice.

Safety Advisory Notice SAN20050012

The Australian Transport Safety Bureau notifies operators of Dash 8 aircraft fitted with part number A44700-007 and/or A44700-009 roll spoiler actuator components, of the increased risk of the cracking and/or rupture failure of the actuator cylinder section as the actuators accumulate service cycles. Failures have been sustained by actuators with service lives ranging from 27,909 to 41,716 cycles. Cracking or rupture of an actuator cylinder results in the loss of contents and subsequent failure of the associated aircraft hydraulic system. Given that the loss of an aircraft hydraulic system will result in extended landing distance requirements, operators are advised to consider the safety implications of operating affected aircraft to regions where the increased landing distance requirements may not be easily accommodated by available primary or alternate aerodromes.

Analysis

ANALYSIS

Actuator failure

The investigation determined that the roll spoiler actuator from TNG had failed as a result of the growth of fatigue cracking from within the actuator cylinder. Originating from the internal threads at the end of the cylinder, the cracking propagated under service pressure cycles to a point where it compromised the cylinder wall and subsequently caused the rupture of the housing.

ATSB research found records of 16 actuator failures within the world fleet, of the type and nature sustained by TNG. All such failures had occurred in part number A44700-007 or -009 actuators and all had occurred in units that had accumulated over 27,000 flight cycles. There was no record of failures of the newer part number 1556000-1 actuators.

On the basis of the investigation findings, it was apparent that the design of the A44700-007 and -009 actuators renders the units susceptible to fatigue cracking and failure under service conditions. The nature of design influenced fatigue failures is such that they typically present a range of cycles-to-failure that is characterised by a lower threshold value and an increasing number of failures as cumulative cycles increase. The distribution of known actuator failures reflects these features and as such, it is a reasonable expectation that the number of future failures will increase with the age of the Dash 8 fleet equipped with the A44700 series actuators.

Operational implications

Following the TNG actuator failure and increasing awareness of the actuator deficiencies, the aircraft manufacturer reviewed the issues from a risk management perspective and elected not to pursue any direct course of safety action, on the basis that the probability and risks presented by the events were low. From the information available, it was not apparent whether the aircraft manufacturer, in its decision not to implement any direct safety action, had considered the likelihood of an increasing frequency of actuator failure as the number of component flight cycles build across the fleet. Nor is it known if the manufacturer had considered the performance implications of actuator failure and hydraulic system loss where the aircraft was being operated into areas with limited runway distance availability.

Summary

Shortly after reaching a cruising altitude of 12,000 ft (FL120), the flight crew of a de Havilland Canada DHC-8-102 (Dash 8), registered VH-TNG, that was operating a scheduled passenger service from Brisbane to Roma (Queensland), were alerted to the failure and rapid loss of contents from the number-2 hydraulic system. Electing to return the aircraft to Brisbane, the flight crew carried out the relevant quick-reference handbook (QRH) checks, and after some initial difficulty, manually extended the landing gear.

Occurrence summary

Investigation number 200303861
Occurrence date 06/09/2003
Location Brisbane, Aero.
State Queensland
Report release date 01/02/2006
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Hydraulic
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer De Havilland Canada/De Havilland Aircraft of Canada
Model DHC-8
Registration VH-TNG
Serial number 041
Sector Turboprop
Operation type Air Transport High Capacity
Departure point Brisbane, QLD
Destination Roma, QLD
Damage Nil

Aerospatiale AS.332L, VH-BHY

Safety Action

Local safety action

Immediately following the incident, the helicopter operator changed the tail rotor pitch change shaft bearings in all of the AS332L helicopters in its fleet. Subsequently, the operator issued Alert Message AM/332/03/008 to all of its local and international facilities, instructing maintenance personnel to immediately change the pitch change shaft bearings should they have been contaminated by hydraulic fluid, or should any doubt exist as to the bearing's condition.

On 5 November 2003, the aircraft manufacturer issued Information Telex 00000151, alerting all operators of AS332, AS330 and AS532 aircraft of the subject incident and instructing maintenance personnel to check the tail rotor pitch change bearing if any fluid leak is discovered at the tail rotor servo actuator. Subsequently, Alert Telex 00000158 was issued on 8 December 2003 requiring 10-hourly inspections for hydraulic leaks at the tail rotor boot and detailing a new mandatory maintenance procedure to be applied should a leak be discovered. Due to an error in the original Alert Telex, an erratum document (Alert Telex 00000166) was issued on 19 December 2003.

On 26 February 2004, the Direction Gnrale de l'Aviation Civile France ( DGAC) issued airworthiness directive (AD) No. F-2004-031, mandating the 10-hourly inspection of the AS332 tail rotor hub boot for evidence of hydraulic fluid leakage. If fluid leakage is discovered, replacement of the pitch-change shaft bearing is required. The Australian Civil Aviation Safety Authority subsequently issued AD/S-PUMA/51 on 26 February 2004, mirroring the requirements of AD F-2004-031 for aircraft in the Australian fleet.

1 Right-hand thread, clockwise rotation to tighten.
2 Counter-clockwise to tighten.
3 The aircraft manufacturer identified the bearing grease as Aeroshell-33 universal airframe grease (MIL-PRF-23827C Type 1).
4 Specified as Aeroshell fluid 41 (MIL-PRF-5606H).
5 Anexus Laboratories, Bulleen Victoria. Report No. C1110 "Assessment of Bearing Grease for Possible Contamination".

Significant Factors

The following factors were identified as significant to the development of the incident.

  1. The tail rotor control servo unit developed a hydraulic fluid leak, with some of the lost fluid entering the pitch change shaft bearing space.
  2. Migration of hydraulic fluid into the bearing diluted the grease, affecting the lubricant efficacy and producing accelerated wear and break-up of the bearing cage.
  3. The bearing grease was soluble in the hydraulic fluid.
  4. The bearing was allowed to remain in service following the discovery and rectification of the hydraulic leak.
  5. The pitch change shaft inboard (servo end) nut was a conventional ( right-hand) thread, allowing it to be loosened and unscrewed by torque from the rotating tail rotor drive shaft.
  6. Disconnection of the pitch change shaft from the servo actuator caused control of the tail rotor to be lost.

Analysis

The investigation found that the loss of tail rotor control reported by the flight crew of VH-BHY occurred as a result of the disconnection of the tail rotor pitch change servo from the control rod. That disconnection was a direct result of a breakdown in the anti-friction properties of the tail rotor pitch change shaft bearing, allowing the rotational torque along the pitch change shaft to overcome the assembly torque and locking assembly of the servo end shaft nut. The rotating shaft subsequently unscrewed the nut, allowing it to drop into the tail structure from where it was recovered.

The tail rotor pitch change shaft bearing failure occurred as a result of the contamination and dilution of the grease lubricant, leading to the internal mechanical breakdown of the bearing cage and the partial seizure of the assembly. Testing showed that the bearing grease was contaminated by hydraulic fluid, which likely released from a leaking tail rotor servo-actuator unit identified and replaced 22 days before the incident. The bearing was inspected at the time of the leak discovery and was found to be satisfactory for further service. At that time, there was no requirement to change the bearing in the event of the leakage of hydraulic fluid into the bearing space.

Summary

History of the flight

At approximately 1715 on 29 August 2003, the crew of a Eurocopter AS332L 'Super Puma' helicopter, registration VH-BHY, being operated on an offshore commuter flight from Karratha, Western Australia, reported feeling a sudden airframe jolt, followed by a pitch up, roll, and a left yawing motion. Finding they had lost tail rotor control, the crew stabilised the aircraft using pitch and roll control inputs, before declaring a MAYDAY to air traffic services. After assessing the helicopter's condition and vibration levels, the crew elected to return to Karratha where a run-on landing could be performed. The MAYDAY condition was downgraded to a PAN and, after assessing the helicopter's performance during a precautionary approach, a safe run-on landing was conducted.

The aircraft was carrying a flight crew of two and six passengers who were uninjured.

Damage to the aircraft

Damage to the helicopter was limited to the tail rotor pitch change assembly and the tail boom lower keel fairing, which had pulled out several attachment screws. During the initial post-incident inspection, the operator's ground maintenance personnel found the nut and lock washer disconnected from the servo end of the pitch change rod, allowing the rod to move freely within the servo body. The nut and washer were subsequently found in the tail structure beneath the tail rotor drive shaft. The rod (P/N 332A33-0043-00) had sustained circumferential gouging and scoring around the surfaces adjacent to the inboard side of the pitch change spider bearing (P/N 330A33-9903-20). The bearing itself showed evidence of gross mechanical failure, with break-up of the ball cage and dislodgement of the outboard and inboard seals. The outboard bearing retention nut and lock washer remained in-place and secure (figure 2).

Aircraft information

Manufacturer Aerospatiale (Eurocopter)
Model AS332L 'Super Puma'
Serial Number 2129
Registration VH-BHY
Year of manufacture 1984
Total airframe hours 13,525 (approx, at time of incident)

Tail rotor assembly information

The Super Puma helicopter tail rotor control was effected by a hydraulic servo-actuator that applies control force to the tail rotor blades via a central shaft and spider assembly. A locking nut and lock washer secured the actuator to the shaft, assembled to a nominal 266 - 443 pound-inches ( 30 - 50 Newton-metres) dry torque. At the spider end, the connection was similar, with a nominal dry torque of 115 - 266 pound-inches (13 - 30 Newton-metres). The Super Puma tail rotor turns in a counter-clockwise direction when viewed from the right side of the aircraft. The securing nut on the servo end of the pitch change shaft had a conventional thread, while the nut on the spider end of the rod had a left-hand thread. Figures 3 and 4 illustrate the tail rotor assembly and pitch change shaft location.

Maintenance history

The failed tail rotor bearing was first fitted to VH-BHY in June 2000, as part of a complete replacement tail rotor gearbox (TRG) assembly. The gearbox, including bearing, had 199 hours time since overhaul (TSO) when installed. Replacement of the pitch change bearing is normally carried out during gearbox overhaul, however documentation to confirm that action was not available to the investigation.

In June 2003, maintenance action was carried out on the gearbox in response to elevated lateral vibration levels recorded by the helicopter's integrated health and usage monitoring system (IHUMS). Subsequently, on 7 August 2003, the tail servo was replaced after the discovery of leaked hydraulic fluid inside the boot between the tail rotor hub and the pitch change spider. It was evident that the fluid had travelled from the tail servo, through the tail rotor drive shaft and into the boot, bringing the fluid into close proximity with the inboard end of the tail rotor pitch change shaft bearing. The gearbox and assembly had accrued 1,888 hours TSO at that time. During the weeks following the hydraulic leak, the pitch change shaft bearing was inspected as required by service bulletin SB05-00-29 Rev. 3 and accepted for further service. At the time of failure on 29 August 2003, the TRG and pitch change shaft bearing had operated for 1,959 hours since overhaul.

Bearing failure

The bearing fitted to the tail rotor pitch change assembly on VH-BHY was a single race, fully sealed ball bearing, manufactured by SNFA, France. The bearing carried the following identifying marks:

330A33990320 8020141 SNFA FRANCE V80I24K14

ATSB laboratory examination of the bearing confirmed the mechanical failure and break-up of the bearing cage, allowing the circumferential movement of the balls relative to each other and the resultant development of abnormal race loading and frictional conditions (figure 5). The bearing internal surfaces were dry and in most places covered with an adherent black compound (figure 6) that was sampled for later analysis. There was no evidence of any viscous bearing grease remaining within the bearing confines. All rolling contact surfaces of the bearing showed bruising and particle indentation damage (figure 7), however there was no indication of spalling or other rolling contact fatigue type breakdown. None of the bearing components showed evidence of gross overheating or frictional seizure. The bearing cage showed gross levels of wear and metal loss in areas exposed to contact with the rolling elements (figure 8 ). Several fracture surfaces showed evidence of fatigue cracking. The external surfaces of the bearing outer race showed fretting corrosion and wear to the extent of seating within the pitch change spider assembly ( figure 9). There was no evidence of circumferential scoring or other indications of race rotation within the housing or on the bearing seat. Traces of light oil were found on the bearing seat. The odour and appearance of the oil were typical of hydraulic fluid.

Bearing construction

The ATSB examined the tail rotor pitch change bearings from two other AS332L helicopters maintained by the same operator. Both of those bearings and their integral seals were found to be in serviceable condition and showed none of the characteristic indications of failure presented by the bearing from VH-BHY. The service lives of both examined bearings were comparable to the failed unit from VH-BHY. A sample of grease from one of the serviceable bearings was subject to a solubility test with a small quantity of hydraulic fluid recovered from the tail rotor servo fitted to VH-BHY at the time of the incident. With a small amount of manual agitation, the grease proved miscible within the hydraulic fluid, producing a liquid with a characteristic viscosity not appreciably greater than the original hydraulic fluid. Weighing the bearing before and after cleaning found the unit carrying 1.88 grams of grease, which the aircraft manufacturer indicated was a nominal quantity.

Bearing contaminant analysis

Samples of the remnant lubricant from inside the failed bearing, the uncontaminated grease from a serviceable bearing and the hydraulic fluid from VH-BHY were forwarded to an analytical laboratory to determine whether any trace of the hydraulic fluid could be detected within the material from the failed bearing.

Results from that analysis confirmed the presence of characteristic spectral peaks from the hydraulic fluid to exist within the remnants of the grease from the failed bearing. These peaks did not exist within the sample of uncontaminated grease from the serviceable bearing.

Occurrence summary

Investigation number 200303804
Occurrence date 29/08/2003
Location North Rankin A Platform, (HLS)
State Western Australia
Report release date 24/05/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Propeller/rotor malfunction
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Aerospatiale Industries
Model AS332
Registration VH-BHY
Sector Helicopter
Operation type Charter
Departure point Karratha, WA
Destination North Rankin A offshore platform
Damage Minor