Boeing 717-200, VH-VQB

Safety Action

As a result of this occurrence, the aircraft operator advised the ATSB that it had initiated a number of immediate safety initiatives to prevent a recurrence, including:

  • Issuing a notice to all contracted ground handling staff requiring that the correct controller/PPU combination be cross checked by two staff members prior to push back operation commencing. It was intended that process would no longer be required once the long term actions have been implemented.
  • A reassessment of all PPU operators was carried out by a manufacturer approved trainer. This training and assessment was documented in accordance with the contracted company procedures.
  • Permission from the flight crew must be obtained prior to connecting PPUs to aircraft (in addition to asking for the park brake to be set). This is designed to reinforce the connection between connecting the PPU to the aircraft and the need for the park brake to be set.
  • The engine of the PPUs is to be stopped after connection to the aircraft and started prior to push back using the remote control. This ensures that the first remote control command is not a commanding movement.
  • Lockable boxes are to be installed on the PPUs to house the remote control units. The controllers remain with the PPU at all times.
  • PPUs and controllers have been colour coded and large numbers placed on the PPUs to allow quick visual identification.
  • The PPU manufacturer is to be asked to consider an engineering solution that prohibits the use of the incorrect remote control being used to inadvertently move an aircraft.
  • The function of the remote control communication indicator lights is to be included in training syllabi and procedure documentation.
  • The newly fitted test button on the remote control is utilized as a safeguard by requiring the operator to test the remote communication prior to beginning each push back operation.
  • Consideration be given to requesting the manufacturer to change the control logic to require the test button to be used in the period shortly before the push or pull button action.

Summary

The Australian Transport Safety Bureau did not conduct an on-scene investigation of this occurrence. The report presented below was prepared principally from information supplied to the Bureau.

REPORTED INFORMATION

At 1855 on 21 June 2004, a Boeing 717-200 aircraft, registered VH-VQB, was being prepared for departure at gate 49 at Sydney Airport. At the same time, another company Boeing 717-200 aircraft, registered VH-VQE, was being prepared for departure at the adjacent gate 53.

Both aircraft had been prepared for pushback and had remote control Power Push Units (PPU) positioned on the respective aircraft main landing gear. VQB was in the final stages of preparation for departure with all ground service equipment clear of the aircraft, all passengers on-board and seated with door 1 Left (L1) open and the aerobridge connected to the aircraft. The cabin service manager was completing documentation in the aircraft near door L1, and two customer service officers were located on the aerobridge.

VQE was ready for departure ahead of schedule and the flight crew received a pushback clearance. They then advised the ground crew that the aircraft was 'clear to push'. A push back was commenced by a ground crewmember, using a hand-held remote control unit, however the PPU did not respond to the ground crew's command to commence reversing. The ground crewmember, initially believing the remote control unit battery was discharged, replaced the battery and attempted a second pushback without success.

aair200402287_001.jpg

At the time the command to pushback was sent to the PPU attached to VQE at gate 53, VQB began to move rearwards at gate 49. The flight crew of VQB, sensing the unexpected movement, immediately applied the aircraft brakes; however, the aircraft had moved rearward more than a metre. As the aircraft moved, the two customer service officers in the aerobridge became unsteady on their feet and a flight attendant in the aircraft galley received a minor scratch on one arm. Once the aircraft was stopped and secured, all passengers were disembarked through door 1 Right using portable stairs.

A subsequent examination of the aircraft revealed that VQB had been damaged as a result of contact between the aircraft and the aerobridge. The left angle of attack vane was bent, there was some minor skin damage around the angle of attack vane mounting and the L1 door trim was damaged. The damage was repaired and the aircraft was returned to service the following day.

Aircraft Ground Handling

Ground handling services for the aircraft operator were provided by a contracted ground handling agent. The agent owned and operated the PPUs and trained staff in their operation. The PPUs were attached to the aircraft main landing gear and provided motive force for aircraft pushback without the need for a towbar. The PPUs were activated via a hand-held remote control unit. The remote control units had an operating range of approximately 100 metres and were digitally encoded to ensure that the remote control unit would only operate its assigned PPU. The two PPUs and controllers used by the operator in Sydney were marked with matching serial numbers and two amber lights would illuminate on the PPU when any remote control button was pushed, signifying that the PPU was the one being activated.

At the time of the occurrence, the ground handling crews for gates 49 and 53 had inadvertently obtained the incorrect remote control units for their respective PPUs prior to the commencement of aircraft pushback.

Occurrence summary

Investigation number 200402287
Occurrence date 21/06/2004
Location Sydney, Aero.
State New South Wales
Report release date 27/04/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Taxiing collision/near collision
Occurrence class Incident
Highest injury level Minor

Aircraft details

Manufacturer The Boeing Company
Model 717
Registration VH-VQB
Serial number 55002
Sector Jet
Operation type Air Transport High Capacity
Departure point Sydney, NSW
Destination Coolangatta, QLD
Damage Minor

McDonnell Douglas MD 520N, VH-MPI

Significant Factors

  1. The drag brace bushing did not comply with the helicopter manufacturer's specifications.
  2. The drag brace bushing hole had a rough-surface finish.
  3. The drag brace bushing was not fitted using protective coating material.
  4. Fatigue cracking initiated in the bore of the drag brace bushing hole.
  5. The right rear strut fractured during the landing.


Technical Analysis

MD Helicopters, Model MD520N, VH-MPI, 21 June 2004

Examination brief

The right front and rear landing gear strut assemblies from the helicopter (without fairings) were submitted to the ATSB's Canberra Technical Analysis Laboratory for examination and analysis of the failures. The parts were identified as follows:

Front strut:91 - 369H 6001-42 D
Rev. 6 1-24-91
S/O. A0201132
Rear strut:PNo: 369H 6001-32

The front strut carried the identification as ink stencilled print on the elbow section of the assembly. The rear strut did not carry any permanent markings and was identified solely by reference to the attached tag.

Summary

The aircraft coordinated estimate RIGMI at 0338 UTC. The aircraft passed seven minutes late, nil details were passed on from the New Zealand control centre.

At about 0630 Eastern Standard Time on 21 June 2004, a MD Helicopters MD520N helicopter, registered VH-MPI, took off from Gladstone, Queensland, to transport a marine pilot to the deck of a bulk carrier ship that was preparing to enter Gladstone harbour. During the landing on the ship, the right landing gear struts fractured. The helicopter collapsed onto its right side and the main rotor blades struck the ship's deck. The helicopter was substantially damaged and the pilot and passenger exited the helicopter uninjured.

The pilot satisfied Civil Aviation Safety Authority (CASA) recency requirements and was familiar with both the helicopter and the mission to be flown. He reported that he had conducted over 100 deck landings and was familiar with landing on ships of the type involved in the occurrence.

The pilot reported that weather conditions were fine with a clear sky, temperature about 17 degrees Celsius, wind from the south-west at about 25 knots, and a slight sea state.

The ship had a number of large hatches aligned longitudinally along the deck. The pilot was using one of those hatches as a landing area. The hatch was of a suitable size to accommodate the helicopter and there were no obstructions in the vicinity of the landing area. The pilot reported that the ship was underway and steaming at about 10 knots. The ship sustained minor damage to the hatch from main rotor blade impact.

The helicopter was fitted with a fixed utility float installation system on the landing gear. The floats had been fitted to the helicopter in July 2001 in accordance with the instructions contained in a CAR 35 engineering approval. The helicopter manufacturer was not able to provide engineering advice on the effect that the float installation would have had on the helicopter.

The primary damage to the helicopter was confined to the landing gear; in particular, the right front and right rear struts, and the main rotor assembly. A metallurgical examination of the landing gear components identified an existing fatigue crack, emanating from the drag brace attachment lower hole in the strut, as an initiation site for the failure of the right rear strut. The fatigue crack was due to the fitment of a non-standard drag brace bushing to the rear landing gear strut. The drag brace bushing also was not fitted using protective coating material and would not have been provided with corrosion protection from the marine environment. The right front strut failed in gross overload. A copy of the technical analysis investigation report, BE200400015, is at Appendix A.

Examination of the helicopter's maintenance documentation revealed the following:

  • The helicopter had a valid maintenance release for the flight.
  • The landing gear fairing fillets were removed and the landing gear was visually checked for cracks and damage during 100-hourly/annual inspections. The last 100-hourly inspection prior to the occurrence was conducted on 3 June 2004.
  • Every 300 hours a landing gear inspection was carried out in accordance with the helicopter's maintenance manual. Those inspections required that the helicopter be jacked and the landing gear checked. Any elongated, enlarged or worn holes in the strut were to be repaired. The last 300-hourly inspection prior to the occurrence was conducted on 3 June 2004.
  • There were no CASA or US Federal Aviation Administration Airworthiness Directives applicable to the 520N helicopter that would have required an inspection of the affected area to check for defects such as cracking of the strut.
  • All required landing gear periodic and special inspections were carried out.
  • Other than routine inspections, no maintenance action had been conducted in the region of the failure.
  • No record could be found to indicate when the non-standard drag brace bushing had been fitted to the rear landing gear strut.

Occurrence summary

Investigation number 200402243
Occurrence date 21/06/2004
Location 30 km E Gladstone, Aero.
State Queensland
Report release date 06/06/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Landing gear/indication
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer McDonnell Douglas Corp.
Model 520
Registration VH-MPI
Serial number LN026
Sector Helicopter
Operation type Aerial Work
Departure point Gladstone, QLD
Destination MV Energy Angel underway
Damage Substantial

Cessna 150F, VH-DDQ

Summary

The Australian Transport Safety Bureau did not conduct an on-scene investigation of this occurrence. The information presented below was obtained from information supplied to the Bureau.

At about 1130 Eastern Standard Time on 20 June 2004, the Cessna 150F departed runway 28 at Gladstone, Qld for a local flight. As the aircraft climbed through 200 ft above ground level, the engine began to lose power. The pilot selected the fuel shutoff valve to OFF for a forced landing on a nearby road. During the landing, the aircraft's right wing struck an embankment and the aircraft sustained substantial damage. The two occupants received minor injuries.

The pilot later reported that the aircraft had been washed about two hours before the flight, and had departed with 35 litres of fuel in the tanks. Meteorological information indicated that induction system icing was possible but it could not be verified. Similarly, the possibility of water contamination of the fuel system was considered, but could not be substantiated. The reason for the engine failure was not established.

Occurrence summary

Investigation number 200402259
Occurrence date 20/06/2004
Location Gladstone, Aero.
State Queensland
Report release date 03/09/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Forced/precautionary landing
Occurrence class Accident
Highest injury level Minor

Aircraft details

Manufacturer Cessna Aircraft Company
Model 150
Registration VH-DDQ
Serial number 15063461
Sector Piston
Operation type Private
Departure point Gladstone, QLD
Destination Gladstone, QLD
Damage Substantial

Boeing 747-438, VH-OJT

Summary

The Australian Transport Safety Bureau did not conduct an on scene investigation of this occurrence. The information presented below was obtained from information supplied to the Bureau.

On 16 June 2004 at 0540 Coordinated Universal Time, a Boeing 747-438, registered VH-OJT, was being operated on an international passenger flight from Singapore to Sydney, with four pilots on board. During the cruise, the co-pilot reported back pain and became incapacitated and was unable to return to duty after crew rest. The co-pilot was relieved of duty and the flight continued to the destination with the pilot in command and one of the other pilots at the controls.

Occurrence summary

Investigation number 200402232
Occurrence date 16/06/2004
Location Ildam, (IFR)
State International
Report release date 30/06/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight crew incapacitation
Occurrence class Serious Incident
Highest injury level Minor

Aircraft details

Manufacturer The Boeing Company
Model 747
Registration VH-OJT
Serial number 25565
Sector Jet
Operation type Air Transport High Capacity
Departure point Changi, Singapore
Destination Sydney, NSW
Damage Nil

Bell 206B (II), VH-PHF

Safety Action

Civil Aviation Safety Authority safety action

Early in the investigation, consultative briefings were held between the Civil Aviation Safety Authority (CASA) and the ATSB. As a result of those briefings, CASA wrote to all Bell 206 operators on 11 August 2004, to raise awareness among those operators who had KAflex driveshafts installed in their helicopters of the ongoing inspection and maintenance requirements, and the warnings listed in the STC. This was done to ensure that operators using KAflex driveshafts incorporated the STC requirements into the appropriate periodic maintenance schedules and flight manuals for the affected helicopter on the Australian civil register.

Manufacturer safety action

Throughout the investigation, the manufacturer worked cooperatively with the ATSB to address the deficiencies identified. The manufacturer has advised that to date they have:

  1. Changed the STC manual and included advice on the correct use of the historical service card. These changes, when approved, will be distributed as a revised Service Instruction to all operators using the STC

     
  2. Reviewed the layout of the historical service card to determine if the format can be amended to include a section specifically for 1500-hourly helicopter inspections

     
  3. Included warning notices in the flight manual supplement for the helicopter about red dust residue and turning fasteners

     
  4. Advised that, although they intended the daily inspection of the KAflex shaft to be a maintenance personnel action, the flight manual supplement would be produced for incorporation into the approved flight manual (AFM) for use by aircrew operating helicopters that have the STC incorporated.

Because the format of the historical service card, STC wording and AFM supplement are US Federal Aviation Administration approved, any changes made to these documents will be submitted to that regulator for final approval.

Operator safety action

The operator advised that the company had manufactured and was fitting a stainless-steel placard to the engine firewall which would be in clear view when personnel opened the inspection panel. This placard would be adjacent to the KAflex driveshaft and would read "KAflex Driveshaft - Daily Inspection" and list the STC warning and inspection requirements. This placard would be fitted to any helicopter operated by the company that is fitted with a KAflex shaft or to any helicopter subsequently retrofitted with one.

The operator also advised that they would introduce and use a supplementary logbook for the driveshaft and that it would always accompany the aircraft logbooks. They would also instigate a program to highlight to company flight and maintenance personnel the differences between KAflex and non-KAflex equipped machines and the consequent maintenance and inspection requirements.

The Bureau will continue to monitor all proposed actions taken to prevent similar occurrences and subsequent evidence to address the deficiencies, when received, will be published on the ATSB website.

Analysis

The KAflex shaft had been fitted in accordance with the published requirements in the supplemental type certificate (STC) about 6 years, or 4,112.35 flying hours, prior to the occurrence. As far as could be determined, no certifications had been made that the shaft had been inspected in accordance with the STC inspection requirements during that period.

There was no flight manual supplement supplied as part of the STC, which would have alerted pilots to the specific inspection requirements and the significance of red dust production. As well as the daily inspection requirements for the shaft, the supplement did not include the warning not to disturb the bolts and to reject a shaft that showed evidence of turning of the fasteners.

The STC documents supplied with the shaft were not kept with the current helicopter logbook, although it was readily available. The retention of the STC documents in the archived logbook, instead of the current logbook, meant that the STC inspection requirements were overlooked and consequently not actioned by maintenance personnel. That resulted in the STC inspection requirements not being included as part of the routine or scheduled maintenance paperwork packages when they were assembled for release to service maintenance events.

The historical service record card for the shaft could not be located and had not been included in the helicopter records as required by the manufacturer in the STC accomplishment instructions. The minimal reference made to the card in the STC could easily have lead to the card being overlooked. When an example of the card was obtained, the appropriate location for the certification of maintenance activities was not readily apparent. The lack of a specific area on the card to certify completion of maintenance may have also contributed to the non-use of the card by maintenance personnel, including the 1500-hourly inspection certification in the airframe logbook. Also, inclusion of these inspection certifications in the airframe logbook could lead to the certification history for a driveshaft being lost if a driveshaft was subsequently moved from one helicopter to another. When overhaul became due, this service history would also have been unavailable to the manufacturer when the shaft and accompanying historical service card were returned to them.

The shaft failure had been initiated by fretting type movement at a flex frame bolted joint. This progressed until the joint failed, resulting in the gross overload failure of the remaining frames. That movement, in its early stages, should have been detectable by the presence of the red dust or loose bolted joints described in the STC inspection warnings. Had the maintenance and operating personnel been aware of the STC inspection schedules, they would have had a better understanding of the significance of the red dust and its ramifications.

Although the operator submitted that his personnel would have detected red dust had it been present around the flex frame joints, the wear pattern evident on the flex frame joint in Figure 1 was consistent with the flex frame fastener being loose for a period of time prior to the failure. The loose bolted joints were not detected. In this occurrence, the loss of bolted joint integrity may have progressed past the point where dust production may occur.

Summary

At 1702 central standard time on 14 June 2004, a Bell Helicopter Company 206B(II) Jetranger, registered VH-PHF, was being operated for a medical evacuation from Deep Well, NT, to Alice Springs. About 5 NM south-west of Alice Springs Airport, while cruising at 500 ft above ground level at 100 kts, the pilot felt a vibration and heard a loud bang accompanied by a reduction in main rotor torque. The pilot immediately placed the helicopter into an autorotative descent and broadcast a MAYDAY1 to the Alice Springs Air Traffic Control aerodrome controller. The pilot landed the helicopter in a clearing and the five occupants were uninjured.

Initial inspection of the helicopter by the operator revealed that the KAflex2 driveshaft between the engine free-wheeling unit and the main transmission had failed. The failed shaft and its components were removed from the helicopter and forwarded to the Australian Transport Safety Bureau (ATSB) for metallurgical examination. The examination found that the failures had occurred in the arms of the web elements, with all of the fractures typical of gross-overload failure from either a single or small number of cycles. Of significant interest was the separation of one of the flex frame unions (see Figure 1). This section showed evidence of wear and deformation consistent with looseness of the bolted joint fastener. Fatigue cracking had initiated from the bore or worn surfaces of the frame and propagated radially away from the hole, intersecting the side of the frame and freeing the connection.

Figure 1: Worn fastener bore and fracture in flex frame. Arrows indicate the point
of fatigue crack initiation and the direction of propagation.

aair200402194_001.jpg

Maintenance history

The helicopter's Maintenance Release was valid until 27 November 2004 or 12,351.80 hours in service, whichever occurred first. At the time of the failure, the helicopter had 12,168.25 hours in service. The operator had responsibility for the maintenance of the helicopter, which was conducted under a valid Certificate of Approval. The helicopter was operated in the Normal category, Day VFR.

The helicopter was maintained as a Class B type aircraft, with the airframe maintenance conducted in accordance with the manufacturer's prescribed maintenance procedures. In this instance, the Bell Helicopter Textron Company 206 Maintenance Manual BHT-206A/B-SERIES-MM-1 was identified in the Logbook Statement as the primary documentation. However, the driveshaft manufacturer's documentation was not identified as required supplemental documentation in that statement. The inspection schedule worksheets for maintenance were copied, for use by the maintenance personnel, directly from the airframe manufacturer's manuals. No supplemental maintenance inspection sheets were incorporated into any of the maintenance worksheet packages that specifically identified maintenance actions to be performed for the KAflex driveshaft.

The helicopter underwent a 300-hourly inspection for the issue of a maintenance release at Moorabbin, Victoria on 27 November 2003. No entries were recorded on the maintenance release with regard to any daily or periodic inspection requirements specific to the KAflex driveshaft.

Main driveshaft

The Jetranger was delivered with a proprietary designed main driveshaft. The driveshaft, which comprised a spherical coupling at either end of a torque shaft, was designed to transmit power from the engine freewheeling unit output adapter to the main transmission input quill. The engine's output shaft speed was around 6,000 RPM3 during helicopter operation. The application of power and flight and ground loads all contributed to drive line misalignment during operation. The spherical coupling design compensated for that misalignment under normal operating conditions. The main driveshaft was subject to ongoing monitoring through heat sensitive temperature indicators that detected overheating caused by inadequate lubrication, wear, or excessive misalignment of the drive train elements. Periodic maintenance of the driveshaft included disassembly, inspection and lubrication in accordance with the Bell Helicopter Textron Company 206 Maintenance Manual, to ensure the continuing airworthiness of the driveshaft.

On 19 January 1998, at 8,055.9 hours aircraft total time in service, the Bell manufactured engine-to-transmission driveshaft in the helicopter had been replaced with a KAflex unit. The new driveshaft was designed to replace the proprietary unit and had been marketed as providing reduced maintenance, longer time between overhauls, and greater reliability.

The Kamatics Corporation web page advised:

Helicopter flight manoeuvres generate high misalignment between the engine and the transmission, which must be accommodated by the connecting driveshaft. Such driveshafts, which rotate at speeds over 6000 RPM, often incorporate grease lubrication and seals. Designs of this type are susceptible to loss of lubrication, which results in overheating and possible failure, a major safety concern.

The KAflex driveshaft is a mechanical drive coupling which requires no lubrication or seals, and transmits power while accommodating high angular misalignment and length change through the use of flexible rectangular frames. These frames are bolted together at the corners in a truss-like arrangement, which are attached to shaft end fittings to allow for drop-in installation in the drive line. A fail-safe feature enables the coupling to continue to transmit power even in the unlikely event of a failure in a load carrying member.

KAflex driveshafts are custom designed for specific applications and selected because they offer superior, maintenance-free performance with extended 'on condition' service-life, resulting in unequalled reliability, increased readiness and cost effectiveness. They are supplied both as individual couplings and as complete driveshafts.

The KAflex driveshaft had been fitted in accordance with Kamatics Corporation supplemental type certificate (STC) SH 7767SW. The helicopter was then ground run and test flown with no defects found. While the KAflex driveshaft remained fitted to the helicopter, the requirements of airworthiness directive (AD)/Bell 206/79 Amdt 14 were no longer applicable to the helicopter.

The STC documentation stipulated that, upon completion of the modifications and installation of the shaft, the historical service record was to be completed, applicable logbook entries made and the card to be kept with the aircraft logbooks. At the completion of its recommended time in service between overhauls, the shaft and the completed historical service card would be returned to the manufacturer for overhaul. While an entry in the helicopter's logbook was made for the installation of the KAflex shaft into the helicopter, no historical service record was found in the helicopter's logbooks pertaining to the shaft.

Maintenance and inspection

A copy of the STC was kept with the archived helicopter logbooks and worksheets, in a separate binder to the current helicopter logbook binder. Both binders were located at the operator's main office. The STC was available to the engineers maintaining the helicopter, but it was not identified by them as a document that they would need to refer to routinely in their maintenance activities.

Although the STC and the manufacturer's website stated that the driveshaft was 'maintenance free' Sections 3 and 4 of the STC detailed the inspection and maintenance regime that the manufacturer expected to be performed while the driveshaft was in service. Section 3 of the STC detailed pre-flight, 100-hourly and 1,500-hourly inspections that were to be performed throughout the 6,000 hour service life5 of the shaft. The inspection advice described examination of the flex frames for the production of 'red dust' showing up as a red metallic residue. Section 3 also contained requirements for a 6,000 hour inspection (which it referred to as maintenance requiring return to the manufacturer) and conditional inspections after specific events, such as an overtorque, an overspeed, a sudden stoppage, a hard landing or a lightning strike. Section 3 also contained the following bold type warning with regard to flex frame attachment hardware:

WARNING
DO NOT disturb or tighten flex frame nuts or bolts. Evidence of turning
fasteners by wrench or other means is cause for rejection.

Section 4 of the STC listed maintenance requirements for the driveshaft. That information stated that there was no periodic maintenance requirement for the KAflex driveshaft.

The operator's managing director stated that at no time did any of his personnel detect the production of red dust residue on the shaft. He also advised that had there been red dust production around the flex frame joints, his personnel would have detected it and prevented the failure. The manufacturer stated that red dust is usually produced in the initial stage of loss of integrity of the bolted joints, but noted that this was not always the case and operators should be vigilant with regard to inspection for loose bolted joints.

From the time of installation of the shaft on 19 January 1998 to the time of the occurrence on 14 June 2004, there were no entries detailing the conduct of periodic or 1,500-hourly inspection certification requirements of the KAflex driveshaft in the helicopter's logbooks, or in the worksheets for maintenance for the issue of a maintenance release. This represented the 4,112.35 hours in service for the KAflex driveshaft. However, there was no stipulation in the STC Section 3 instructions to require certification for the completion of the inspections detailed in that section.

There was also no amendment insert in the helicopter's flight manual for the daily inspection as described in the STC, Section 3 - DAILY INSPECTION BEFORE FIRST FLIGHT OF THE DAY. There was also no stipulation in the STC that the flight manual should be amended in order to make that information readily available to the pilot.

When interviewed, the pilot in command was asked to describe the execution of a daily inspection of the helicopter. While a detailed explanation was given to the interviewer, at no time was the driveshaft manufacturer's warning caveat mentioned or alluded to by the pilot. As this is a bold type warning in the manufacturer's documentation, it should have been a recall item readily identified during this discourse.

Historical service record

There was minimal reference made to the historical service record in the STC. A copy of the card was obtained from the local Australian distributor for KAflex. There was no provision on the card for certification of the 100-hourly and 1,500-hourly inspections. The historical service record card had not been incorporated into the maintenance records for the helicopter as required by the manufacturer in the accomplishment instructions of the STC.

1 International radio broadcast for urgent assistance.
2 A proprietary name for a driveshaft manufactured by a Unites States company, Kamatics Corporation.
3 Output shaft speed at 100% main rotor RPM.
4 AD/Bell 206/79 Amdt 1 detailed the inspection and installation of a Visual Aid Overheat Indicator on a Bell manufactured main input drive shaft assembly. It was later cancelled as those requirements were incorporated into the 100-hourly maintenance servicing requirements.
5 At the time of shaft installation, the STC stipulated a 4,000 hour service life. Service Instruction 2348 Revision "E" dated September 1999 extended this service life to 6,000 hours between overhauls.

Occurrence summary

Investigation number 200402194
Occurrence date 14/06/2004
Location 9 km SW Alice Springs, Aero.
State Northern Territory
Report release date 24/05/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Transmission and gearbox
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Bell Helicopter Co
Model 206
Registration VH-PHF
Serial number 1926
Sector Helicopter
Operation type Aerial Work
Departure point Deep Well, NT
Destination Alice Springs, NT
Damage Minor

Hiller Aviation UH-12E, VH-HMT

Safety Action

As a result of this occurrence, The Australian Transport Safety Bureau (ATSB) draws to the attention of Australian operators of Hiller UH-12E helicopters, the difficulties associated with inspecting the horizontal stabiliser spar tube assembly.

The ATSB has also advised the Civil Aviation Safety Authority of the difficulties associated with inspection of the horizontal stabiliser spar tube assembly and will circulate copies of this report to all Australian operators of Hiller UH-12E helicopters.

Factual information

FACTUAL INFORMATION

On 15 June 2004, a Hiller Aviation UH-12E helicopter, registered VH-HMT, crashed during an agricultural operation, after the pilot reported a loss of tail rotor authority. The pilot was not injured in the accident. The horizontal stabilizer was found about 150 m from the wreckage site, indicating that it had separated from the helicopter in-flight. The operator reported that damage to the stabiliser and the tail rotor blades was consistent with the separated stabiliser coming into contact with the tail rotor blades, as it was still connected to the helicopter by the taillight wiring. The operator reported that an engineering examination found no evidence of tail rotor system failure.

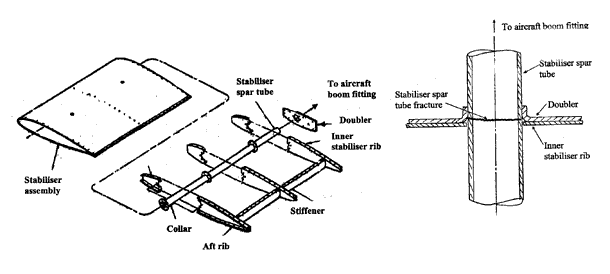
The horizontal stabiliser spar tube failed in the area where the tube passes through a collar in the doubler attached to the inner stabiliser rib (refer to figure 1).

Figure 1: Horizontal stabiliser and detail of the spar tube and doubler.

aair200402215_001.gif

Helicopter

The helicopter was manufactured in 1978 and had accumulated 6,903.50 hours time in service at the time of the accident. In September 2002, at 6,386.25 hours in service, it sustained major damage following a sudden main rotor stoppage. The helicopter was rebuilt and had since accumulated approximately 517.20 hours in service. It was maintained in accordance with the maintenance requirements applicable at the time and had a valid Maintenance Release. It had flown approximately 31 hours since the last periodic inspection, a 100 hourly inspection completed in May 2004.

Horizontal stabiliser

The operator advised the Australian Transport Safety Bureau (ATSB) that the horizontal stabiliser is not a serial numbered item and its time in service since new was not known. The stabiliser was fitted to the helicopter when it was acquired from its previous owner. During the helicopter rebuild in September 2002, the stabiliser was inspected in accordance with the 100 hourly component inspection guide and the Hiller UH-12E maintenance manual, before being re-installed. The component inspection guide required the stabiliser tube to be inspected for corrosion and security and the maintenance manual detailed the spar tube inspection requirements and wear limits. No anomalies with the horizontal stabiliser were reported at that time.

Spar tube failure

The failed horizontal stabiliser was forwarded to the ATSB for detailed examination. That examination revealed that the stabiliser spar tube fractured as a result of fatigue cracking. The crack initiation occurred at a number of locations where the tubing had been reduced in wall thickness by wear. It was apparent that the wear of the tubing was associated with small scale repeated movement between the stabiliser tube and the doubler attached to the stabiliser's inner rib. There was no evidence of any pre-existing defect present.

A search of the ATSB, United States National Transportation Safety Board and Federal Aviation Administration databases found no reported events involving an in-flight separation of the horizontal stabiliser on similar helicopter types.

Summary

The Australian Transport Safety Bureau did not conduct an on-scene investigation of this occurrence.

Occurrence summary

Investigation number 200402215
Occurrence date 15/06/2004
Location 11 km W Innisfail
State Queensland
Report release date 09/08/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Hiller Aviation
Model UH-12
Registration VH-HMT
Serial number HA3066
Sector Helicopter
Operation type Aerial Work
Departure point Innisfail Quarry, QLD
Destination Innisfail Quarry, QLD
Damage Substantial

Loss of separation between a Boeing 747-400, 9V-SPE and a Boeing 747-400, GC-IVC, on 16 June 2004

Safety Action

Airservices Australia safety action

Airservices Australia included the following modification to the Brisbane Centre local instructions applicable to international HF radio operators:

Relay of communications between ATC and pilots, or between pilots and ATC must be completed within 5 (five) minutes of the message being passed to the AusFIC for relay. Any communications relayed to and from ATC must be passed verbatim.

In the event that a message cannot be relayed within the 5 minutes advice must be provided to the appropriate ATC sector.

Analysis

Communications

The reason the HF operator was unable to establish two-way communication with the crew of IVC could not be determined. A formal procedure for notifying the controller that the HF radio operator could not pass the instruction to the crew of IVC may not have ensured that a separation standard existed, as an incorrect instruction had been issued. However, it may have prompted a more timely reassessment of the situation by the controller. In other circumstances, a formal procedure may alert the controller in sufficient time for action to be taken before separation standards are infringed.

Air Traffic Controller

A review of the controller's training records indicated that he had an adequate understanding of the concept of lateral separation. However, his misapplication of a lateral separation point may have reflected his lack of proficiency due to inexperience in working the particular sector of airspace.

Summary

On 16 June 2004, a Boeing 747-400, registered GC-IVC (IVC), was en-route from Melbourne to Singapore on airway A576. The aircraft was approaching the boundary between the Brisbane flight information region (FIR) and the Bali FIR at flight level (FL) 340. Concurrently, a second 747, registered 9V-SPE (SPE), was en-route from Sydney to Singapore on airway G326. That aircraft was also approaching the boundary between the Brisbane FIR and the Bali FIR at FL 340.

The controller recognised that he had to resolve a potential confliction between SPE and a third aircraft. In resolving that confliction, the controller created a new confliction between IVC and SPE. In response, the controller instructed the crew of IVC to reach FL320 by waypoint ATMAP (see Annex A). That requirement was intended to achieve vertical separation between the aircraft prior to any loss of lateral separation1. However, the required lateral separation point was 94 NM south-east of waypoint ATMAP on airway A576. The incorrect requirement led to an infringement of separation standards.

Following a scan of the air situation display, the controller realised that he had issued an incorrect requirement. The controller then issued a second requirement, via the high frequency (HF) radio operator, for IVC to descend to reach FL320 by 80 NM to the south-east of waypoint ATMAP. The controller reported that this requirement was based on the application of a required navigation performance (RNP) 10 separation standard2. This standard was not authorised for use within the Bali FIR. Upon issuing the requirement, the controller handed over to another controller and went on a scheduled break.

Over a period of 10 minutes and 37 seconds, the HF radio operator made 12 unsuccessful attempts to contact the crew of IVC. The oncoming controller realised that the HF radio operator had not been able to make contact with the crew of IVC. He also realised that RNP 10 was not an authorised standard. By that time the authorised separation standards had already been infringed. The oncoming controller then successfully instructed the crew of IVC to descend their aircraft immediately to FL320, via a controller pilot data link communication3 (CPDLC) message to the crew of another aircraft.

The controller involved in this occurrence had completed his field training in April 2004. A review of his training records indicated that he had approximately five weeks' experience on that sector of airspace. According to his check and standardisation supervisor, the controller demonstrated a satisfactory level of competency on completion of his sector-specific training.

The controller was rostered to work an afternoon shift, which commenced at approximately 1500 eastern standard time. During the shift the controller had a break of one hour, returning to the console at approximately 1930. The incident occurred at 2038. There was no evidence that fatigue played a part in the incident.

Coordination of high frequency radio communications

The controller issued the requirement to the crew of IVC to reach FL320 by waypoint ATMAP while that aircraft was within reliable very high frequency (VHF) radio range. However, when the controller realised the error in the requirement, that aircraft had passed outside VHF radio range. The controller attempted to issue the amended requirement to the crew of IVC through a HF radio operator, because the crew of IVC had not nominated CPDLC on their flight plan as a means of communication with ATC.

The HF radio operator was unable to establish two-way communication with the crew of IVC, to pass the amended requirement, despite repeated attempts. The controller was not aware that the HF radio operator was unable to issue the instruction to the crew of IVC.

The controller did not confirm with the HF radio operator that the instruction had been passed to the crew of IVC, and there was no published procedure requiring him to do so. Although there was a requirement for the HF radio operator to notify the controller that the instruction was not passed to the crew of IVC, there was no formal procedure to facilitate that notification.

1 Lateral separation is considered to exist when there is at least a 1 NM buffer between the possible positions of two aircraft (ICAO PANS-ATM, Chapter 5 in CASA Manual of Standards Part 172 10.8.1.1).
2 For RNP10, the approval process must show that the total navigation system error in each dimension must not exceed +/- 10 NM for 95 per cent of the flight time on any portion of any single flight:
a) the true position of the aircraft must be within 10 NM of the programmed route centre line; and
b) the true distance to way-points must be within 10 NM of the displayed distance to waypoints.' (International Civil Aviation Organization, 1999, Manual on required navigation performance [RNP], second edition, p. 6).
3 Controller Pilot Data Link Communications (CPDLC): A means of communications between a controller and pilot using text-based messages via an ATC data link (Manual of Air Traffic Services, part 10, effective 10 June 2004).

Occurrence summary

Investigation number 200402228
Occurrence date 16/06/2004
Location 174 km SE Atmap, (IFR)
State International
Report release date 10/03/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Loss of separation
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 747
Registration 9V-SPE
Sector Jet
Operation type Air Transport High Capacity
Departure point Sydney, NSW
Destination Singapore
Damage Nil

Aircraft details

Manufacturer The Boeing Company
Model 747
Registration GC-IVC
Sector Jet
Operation type Air Transport High Capacity
Departure point Melbourne, VIC
Destination Singapore
Damage Nil

Boeing 767-338ER, VH-OGN

Summary

The Australian Transport Safety Bureau did not conduct an on scene investigation of this occurrence. The information presented below was obtained from information supplied to the Bureau.

The Boeing 767-338ER aircraft, registered VH-OGN, was conducting an international passenger flight from Jakarta to Sydney, with two pilots on board. During cruise, the first officer became incapacitated, reporting stomach cramps, sweating and nausea. The first officer was relieved of duty and the flight continued to destination with the captain at the controls. After landing, the first officer was diagnosed with a possible gastric virus. He recovered fully within 24 hours and has resumed flying duties.

Occurrence summary

Investigation number 200402152
Occurrence date 09/06/2004
Location Jakarta Soekarno-Hatta, Aero.
State International
Report release date 30/06/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight crew incapacitation
Occurrence class Serious Incident
Highest injury level Minor

Aircraft details

Manufacturer The Boeing Company
Model 767
Registration VH-OGN
Serial number 25576
Sector Jet
Operation type Air Transport High Capacity
Departure point Jakarta, Indonesia
Destination Sydney, NSW
Damage Nil

Cirrus SR20, VH-SJA

Summary

Sequence of events

On 6 June 2004, at about 1520 Eastern Standard Time, the pilot of an instrument flight rules (IFR) Cirrus Design Corporation Cirrus SR20 (SR20), registered VH-SJA, was conducting a practice sector 2 entry to the Cowes VHF omnidirectional radio range (VOR) navigation aid in visual meteorological conditions (VMC). The pilot of a visual flight rules (VFR) Cessna Aircraft Company 172P (C172), registered VH-DXX, was also conducting navigation aid practice utilising the Cowes VOR and non-directional radio beacon. The Cowes navigation aids are 54 NM south-east of Melbourne Airport and the pilots were operating outside controlled airspace but within air traffic control radar coverage.

Approximately 8 NM before Cowes VOR, the SR20 pilot requested traffic information for descent to 2,000 ft. The pilot reported that he was given traffic information by the Melbourne Centre controller on a VFR aircraft at an unverified altitude of 1,900 ft. The SR20 pilot broadcast his intentions on the area frequency, 120.0 MHz and the Phillip Island common traffic advisory frequency (CTAF), 119.1 MHz. The pilot did not receive a response.

While approaching the VOR, the SR20 pilot became aware of an aircraft on a reciprocal track at the same altitude of about 2,000 ft. At about the same time, the C172 pilot saw the SR20. Both pilots took evasive action by making high angle of bank right turns. Reports from the pilots indicated that the aircraft passed in close proximity and it was estimated that the distance between the aircraft was 200 m horizontally and 50 ft vertically. The occurrence was classified both as an Airprox1 and a serious incident.

After the aircraft passed, the SR20 pilot attempted to contact the C172 pilot by radio on 120.0 MHz. There was no response from the C172 pilot. Several minutes later, the C172 pilot contacted the Melbourne Centre controller on 120.0 MHz to request traffic information. The controller provided the pilot with traffic information on the SR20.

The C172 pilot reported that he had 135.7 MHz selected at the time of the occurrence. That frequency was the nominated frequency for operating within 40 NM south and south-east of Melbourne Airport. Consequently, he was unable to hear the inbound radio transmissions of the SR20 pilot and develop an awareness of a possible conflict. The C172 pilot stated that the radio frequency of 120.0 MHz and its boundary was not published on the Melbourne Visual Navigation Chart (VNC) or on the Melbourne Visual Terminal Chart (VTC). It was also unclear on the Enroute Chart (Low Level) (ERC-L) what the appropriate frequency for the Cowes area was. The pilot was uncertain as to what frequency should have been selected when conducting airwork in the vicinity of Cowes VOR.

Before this occurrence, Airservices Australia developed an interim Frequency Planning Chart (FPC), which was promulgated by Aeronautical Information Circular (AIC) H4/04 to all licensed pilots with a current medical in March 2004. The FPC published the appropriate Air Traffic Services (ATS) class E and class G radio frequencies. However, the pilot reported that he did not receive the FPC until sometime during July 2004.

Airservices Australia has announced that it will re-introduce the publication of ATS en route class G and class E radio frequencies and frequency boundaries on Aeronautical Information Publication (AIP) charts effective 25 November 2004. Those charts include visual navigation charts, such as the VTC and VNC, and the ERC-L and Terminal Area Charts (TAC). AIC H13/04 provides further information on airspace and frequency management changes.

The difficulties associated with the see-and-avoid principle and the risk of mid-air collisions have been addressed in the following Australian Transport Safety Bureau reports:

  • Bureau of Air Safety Investigation (1991) Limitations of the see-and-avoid principle (BASI Research Report), Canberra: BASI.
  • Australian Transport Safety Bureau (2004) Bankstown midair collision (Aviation Safety Investigation Report 200201846), Canberra: ATSB.
  • Australian Transport Safety Bureau (2004) Flying training accident at Moorabbin (Aviation Safety Investigation Report 200203449), Canberra: ATSB.
  • Australian Transport Safety Bureau (2004) Review of midair collisions involving general aviation aircraft in Australia between 1961 and 2003 (Aviation Research Paper B2004/0114), Canberra: ATSB.
  • Australian Transport Safety Bureau (2004) National Airspace System Stage 2b: Analysis of Available Data (Aviation Research Report B2004/0076), Canberra: ATSB.
  • Australian Transport Safety Bureau (2003) Airprox incident between Cessna 421 and Boeing 737 (Aviation Safety Investigation Report 200304963), Canberra: ATSB.
  • Australian Transport Safety Bureau (2003) Airprox serious incident between Tobago and Boeing 737 (Air Safety Occurrence Report 200305235), Canberra: ATSB.
  • Australian Transport Safety Bureau (2004) Airprox incident between Lancair and Boeing 737 (Aviation Safety Investigation Report 200401273), Canberra: ATSB.

Related Documents: | Media Release |

1 An Airprox is an occurrence in which 2 or more aircraft come into such close proximity that a threat to the safety of the aircraft exists or may exist, in airspace where the aircraft are not subject to an air traffic control separation standard or where separation is a pilot responsibility.

Occurrence summary

Investigation number 200402065
Occurrence date 06/06/2004
Location Cowes, (VOR)
State Victoria
Report release date 28/10/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Near collision
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Cirrus Design Corporation
Model SR20
Registration VH-SJA
Serial number 1353
Sector Piston
Operation type Private
Departure point Moorabbin, VIC
Destination La Trobe Valley, VIC
Damage Nil

Aircraft details

Manufacturer Cessna Aircraft Company
Model 172
Registration VH-DXX
Serial number 17274568
Sector Piston
Operation type Private
Departure point Essendon, VIC
Destination Essendon, VIC
Damage Nil

Cessna 210N, VH-TFI

Summary

The Australian Transport Safety Bureau did not conduct an on scene investigation of this occurrence. The report presented below was derived from information supplied to the Bureau.

The pilot of a Cessna 210 aircraft, registered VH-TFI, who was the sole occupant of the aircraft, was conducting a freight charter flight to several locations in the Northern Territory.

At Baikal airstrip the pilot added 100 L of fuel to the aircraft's left fuel tank from drum stock stored at the airstrip.

Shortly after takeoff, the pilot selected the left fuel tank. The engine then began to surge and run roughly. After seeking advice from the company maintenance staff, he attempted, unsuccessfully, to identify the problem before landing at Utopia station.

The pilot again sought advice from the company maintenance staff before departing Utopia station. Soon after departure, engine oil sprayed onto the windscreen and the engine caught fire and lost power. The pilot intended to return to Utopia station, but almost immediately, the engine failed completely. During the forced landing in an area of low scrub and scattered trees, the pilot sustained facial injuries and the loss of some teeth, but after regaining consciousness was able to vacate the aircraft unassisted. The aircraft was substantially damaged.

Examination of the aircraft by a company engineer revealed that the engine had failed after sustaining catastrophic damage due to contamination of the aircraft's fuel by Jet A1 fuel. The operator reported that when refuelling the aircraft at Baikal, the pilot inadvertently used a drum of Jet A1 fuel.

The operator advised the ATSB that they have amended their refuelling procedures to preclude a recurrence of this accident.

Occurrence summary

Investigation number 200402060
Occurrence date 04/06/2004
Location Utopia Station, (ALA)
State Northern Territory
Report release date 29/07/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Fuel contamination
Occurrence class Accident
Highest injury level Minor

Aircraft details

Manufacturer Cessna Aircraft Company
Model 210
Registration VH-TFI
Serial number 21064255
Sector Piston
Operation type Charter
Departure point Utopia Station, NT
Destination Alcoota Station, NT
Damage Substantial