Airbus A330-301, VH-QPC

Significant Factors

  1. Unforecast fog developed at Sydney aerodrome after the aircraft passed the flight planned DPA decision point, which had been based on a diversion to Melbourne.

     
  2. By the time the crew became aware of the fog, the aircraft did not have sufficient fuel to proceed to an alternate aerodrome categorised by the operator as suitable for normal operations.

     
  3. When the ATIS was amended at 0554 to include a runway visual range of 800 m, the actual visibility at the touchdown zone of the nominated landing runway, 34L, was greater than that figure.

     
  4. The crew continued to track for an approach to runway 34L at Sydney after the nominated time for a diversion to Canberra.

     
  5. While the crew was manoeuvring the aircraft for an approach to runway 34L at Sydney, the fog moved across the threshold of that runway reducing visibility to below the landing minima.


Safety Action

Airservices Australia

As a result of this occurrence, on 26 November 2004 Airservices advised the ATSB that a review of the AIP and MATS will be conducted. This review will ensure that, when a RVR is quoted in the aerodrome information provided by the controller or detailed in the ATIS, the RVR clearly relates to the runway touchdown zone quoted in the information. Airservices will also incorporate the events of the occurrence into a refresher training module to be used by staff at towers with low visibility operations procedures.

As a result of Airservices? advice of this proposed safety action, the ATSB will continue to monitor its progress until evidence is received of the implementation of the proposed actions.

Bureau of Meteorology

The BoM advised that the occurrence was reviewed at a Fog Workshop on 13 July 2004, which resulted in the establishment of the Forecasting at Sydney Airport? project. The aim of the project is to review the existing forecasting methodologies and guidance material used to predict fog at Sydney aerodrome. The BoM intends to use the results from the review and subsequent real-time testing to implement a structured set of objective guidelines that are intended to improve the accuracy of fog forecasting at Sydney aerodrome.

The project is a joint undertaking by staff from the Bureau?s Sydney Airport Meteorological Unit and the Bureau of Meteorology Research Centre, in collaboration with researchers at Monash and Macquarie Universities. The project team members are currently constructing an expanded climatological database for Sydney aerodrome and reviewing the predictors for fog. The planned completion date for the project is December 2005.

Operator

The aircraft operator advised that staff from its safety department gave a presentation to controllers at the Sydney Terminal Control Unit (TCU) on 15 April 2005. The presentation provided an explanation of the operational aspects of the occurrence to ATC from an operator and flight crew perspective. The operator also advised that the same presentation was given at the Air Traffic Service/Airline Forum held on 20 April 2005. The operator plans to give the presentation to Brisbane and Melbourne TCU controllers later in 2005.

The operator also advised that an article describing the occurrence will be published during 2005 in a newsletter distributed to flight crew.

As a result of this advice of proposed safety actions by the operator, the ATSB will continue to monitor its progress until evidence is received of the implementation of the proposed action.

Related Documents: | Media Release |

Analysis

The aircraft landed at Sydney in weather conditions that were below the specified landing minima. Although a landing in conditions below the specified meteorological minima was permitted under Civil Aviation Regulation 257(5) in an emergency situation, a landing at Sydney only became a necessity after 0618, the latest divert time to Canberra. This analysis examines the development of the occurrence and discusses the factors that influenced the crews decision to continue the approach to a landing at Sydney.

The aircraft departed Perth with sufficient fuel for the flight, based on the current Sydney aerodrome forecast. There was no requirement to divert to Melbourne at the flight planned Designated Point All Engines Operating (DPA), because the forecast weather conditions were not below the alternate minima for a landing at Sydney. However, the aircraft passed the DPA at about the same time as low-level cloud was clearing at Sydney. The dissipation of the cloud resulted in the subsequent unforecast movement of fog over the aerodrome. At 0540 the crew was aware that a fogbank had formed to the north-west of the aerodrome, but the other weather information available to them at that time did not indicate that fog would be a problem for their arrival at Sydney.

After commencing the descent, the crew used weather information provided by controllers and from the onboard datalink when making decisions in response to the deteriorating visibility at Sydney aerodrome. However, during the latter stage of the flight the crew were not provided with all of the weather information that was available to ATC. This reduced the crews situational awareness of the effects of the rapid progression of fog across the runway complex. While information was available via the onboard datalink, the crew was busy setting up for the approach into Sydney and would have had an expectation that ATC would advise of any significant deterioration in the weather conditions.

Although the crew considered that the Canberra 0530 special automated weather observation indicated marginal weather conditions, the reported conditions were just above the applicable alternate minima for an ILS approach to runway 35. Had the crew obtained or been provided with the Canberra 0600 trend type forecast, which predicted that the weather conditions would not significantly vary for the following three hours, they may have been more confident about the weather trend at Canberra.

The declaration of minimum fuel? and reiteration of the requirement to use 16R in the crews PAN broadcast at 0559 indicated their concern about having enough fuel to land at Sydney. However, the crews advice to ATC five minutes later, that their latest landing time was 0618,?? and then we?d need to go straight to Canberra? suggests that they had enough fuel to land at Sydney but were attempting to expedite their arrival to enable an attempted landing while retaining Canberra as an alternate for as long as possible.

This was supported by the pilot in commands statement that the PAN broadcast was made because there was insufficient fuel to proceed to an operator approved suitable aerodrome, ATC were vectoring the aircraft for a holding pattern and the weather conditions at Sydney were deteriorating at an unknown rate. The pilot in command also stated that, without the existence of the PAN broadcast, the crew could not use Canberra because, in accordance with the operator's aerodrome categorisation, this aerodrome could only be used in an emergency.

The crews decision to require an approach to runway 16R was based on runway visual range (RVR) information that did not reflect the actual conditions at the time. Had the crew been aware that the RVR for runway 34L was greater than the landing minima for that runway, they may not have advised ATC at 0556 that they required runway 16R. Without the delay caused by commencing that approach, the crew would probably have landed on runway 34L before the weather conditions deteriorated below the specified landing minima for that runway.

The report at 0614 from the crew of the Boeing 747, that they were visual during the approach to runway 34L, was subsequently supported by the advice from ATC that the RVR for that runway was 2,000 m, which was greater than the landing minima. This information was received by the crew of QPC one minute before the nominated last divert time and, given the pilot in commands statement that Canberra would be a preferred option only in the event of weather conditions deteriorating to below the landing minima at Sydney, probably influenced them to continue tracking to runway 34L rather than diverting the aircraft to Canberra.

Although the crew could see the runway 34R threshold during the ILS approach to 34L, an orbit to enable a change of runway to 34R would have delayed the landing with the risk of a further deterioration in weather conditions at both thresholds. Given that the crew was committed to a landing at Sydney, the decision by the pilot in command to continue the runway 34L approach reduced the risk of conducting an approach at a later time when the visibility was likely to be worse. Use of the autoland system by a trained crew constituted the safest way to conduct a landing in conditions below the specified meteorological minima.

Although the operator calculated that the amount of fuel remaining on the aircraft after the landing was sufficient to proceed to Canberra after an approach at Sydney, the crews fuel calculations were conservative and were performed in a dynamic high workload situation.

The occurrence highlights the significant safety issues that unforecast weather conditions present to aircraft when these conditions occur during the latter phase of flight. During this phase, the remaining fuel on board may limit the options available to flight crews to minimise the effect of the unforecast conditions on the operation of the flight.

The occurrence also highlights the need for information sharing between flight crews and air traffic controllers in a timely manner so that the situational awareness of crews and controllers is maintained at a high level and crew decision making is optimised in dynamic weather situations.

Information sharing between flight crews and air traffic controllers was also a factor in two other occurrences, involving high-capacity aircraft, which were investigated by the ATSB (ATSB investigation reports BO/200100213 and BO/200304400).

Summary

Sequence of events

On 6 April 2004, at about 0625 Eastern Standard Time, an Airbus A330-301 aircraft landed on runway 34L at Sydney aerodrome in weather conditions that were below the applicable landing minima1. The aircraft, registered VH-QPC, was being operated on an instrument flight rules (IFR) scheduled passenger flight from Perth to Sydney. During the latter stage of the flight unforecast fog developed at Sydney aerodrome, which resulted in the deterioration of visibility to below the landing minima.

The flight had been planned using a valid aerodrome forecast for Sydney, which predicted rain showers and visibility greater than 10 km, with 1 to 2 oktas2 of cloud at 1,200 ft and 5 to 7 oktas at 5,000 ft. Those weather conditions were above the Sydney alternate minima3 of 1,479 ft cloud ceiling and 6 km visibility. As there were no operational requirements due to the forecast weather conditions, the flight departed Perth without fuel being specifically carried for a diversion to an alternate aerodrome after an approach at Sydney.

The flight planned ?Designated Point All Engines Operating? (DPA)4, based on a diversion to Melbourne, was the IFR waypoint TOBOB, located 314 NM west of Sydney. Prior to TOBOB the crew obtained the 0400 and 0430 Sydney trend type forecasts (TTF). The TTFs were attached to the Sydney aerodrome weather reports and detailed the weather conditions expected to affect the aerodrome for the 3 hours following the time of the weather report. TTFs were routinely issued every 30 minutes for Sydney aerodrome and the 0400, 0430 and 0500 TTFs all indicated that, at the time of the aircraft?s estimated time of arrival (ETA), the visibility and cloud ceiling at Sydney would be above the alternate minima. The crew did not obtain the 0500 TTF. The aircraft passed the TOBOB position at 0518.

The crew commenced descent for Sydney at 0540 and, at about the same time, air traffic control (ATC) broadcast to aircraft that the Sydney automatic terminal information service (ATIS) had changed to include the remark that there was a fog bank to the north-west of the aerodrome. The ATIS was also reporting visibility greater than 10 km, with 1 to 2 oktas of cloud at 1,000 ft and 3,000 ft. The ATIS consisted of a continuous and repetitive broadcast of pre-recorded information about the actual weather conditions at the aerodrome.

The pilot in command reported that following receipt of the ATIS information, the crew obtained weather information about three aerodromes near Sydney; Williamtown, Richmond and Canberra. These aerodromes were available for use during non-normal operations (see Availability and selection of alternate aerodromes for more information). The pilot in command stated that, at the time, he considered the weather conditions at Williamtown might deteriorate to below the landing minima and Richmond was unavailable as the conditions were below the landing minima. He assessed Canberra as presenting potential difficulties due to the cloud ceiling being just below the alternate minima for runway 17 and just above the alternate minima for runway 35. In addition, the crew estimated that the fuel on board was insufficient to allow them to conduct a missed approach at Sydney and then divert the aircraft to Canberra. The pilot in command also stated that Canberra was a relatively unfamiliar aerodrome and he did not have any Notice to Airmen (NOTAM) operational information about Canberra.

The crew obtained the 0530 Sydney TTF soon after commencing descent. It indicated that, at the time of the aircraft?s ETA, there could be periods of up to 60 minutes when the visibility at Sydney would be 7,000 m in rain showers, with 5 to 7 oktas of cloud at 1,000 ft. These conditions were below the alternate minima, but above the special alternate weather minima of 400 ft cloud ceiling and 2 km visibility that applied to instrument landing system (ILS) approaches at Sydney. The aircraft was fitted with navigation equipment that allowed the use of the special alternate minima.

At 0555, as the aircraft descended through flight level 180 about 60 NM south-west of Sydney, ATC advised the crew that the Sydney ATIS had changed to include a hazard alert. This was in response to unforecast fog that had reduced the runway visual range (RVR)5 to 800 m. The ATIS also advised flight crew to expect ILS approaches to runways 34 Left (34L) and 34 Right (34R). One minute later, in response to that broadcast, the crew advised ATC that they required runway 16 Right (16R) for landing. This was due to the runway 16R ILS category one landing minima of 220 ft cloud ceiling and 800 m visibility being less restrictive than the runway 34L ILS category one landing minima of 270 ft and 1,500 m.

At 0558, ATC advised the crew that there would be a delay due to their requirement for an approach to runway 16R and instructed them to turn onto a heading of 230 degrees (taking the aircraft away from the aerodrome). One minute later, the crew broadcast a PAN6, declaring an urgency condition due to ?minimum fuel, require runway 16R for arrival?. The aircraft was then radar vectored for an ILS approach to runway 16R. The pilot in command stated that the PAN call was made because there was insufficient fuel to proceed to an alternate aerodrome approved by the operator for normal operations, ATC were vectoring the aircraft for a holding pattern and the weather conditions at Sydney were deteriorating at an unknown rate.

At about the same time, the crew of a Boeing 737 on final approach for runway 34L advised ATC that they could see the threshold and the first 1,000 m of the runway. The crew of QPC, being on a different radio frequency, did not hear that information, nor was it subsequently provided to them by ATC.

At 0604, in response to a request by ATC for the crew?s latest acceptable landing time at Sydney, they replied ?? time one eight [0618] and then we?d need to go straight to Canberra?. The pilot in command stated that a diversion to Canberra would have been the selected option only in the event that weather conditions at Sydney had deteriorated to below the landing minima. He also considered that a diversion would only ensure a ?minimum fuel state, at best?, upon arrival at Canberra.

At 0611, when the aircraft was about 17 NM north-north-west of the airport and tracking to intercept the runway 16R ILS localiser, the crew requested information about the visibility at the airport. After receiving a report from an approved observer in a motor vehicle positioned near the runway threshold, ATC advised the crew that the visibility on the runway 16R threshold was 400 m. The crew then requested the visibility on runway 34L. They were advised that the crew of a Boeing 747 approaching runway 34L ?reported visual at 1000 ft and he?s been visual all the way to 34L?. The crew of QPC then requested a vector ?for short final 34L? and were provided with radar vectoring for an approach to runway 34L.

The Boeing 747 landed on runway 34L at about 0614 and its crew reported to ATC that ??we were visual the whole way to touchdown, but I?d say this vis [visibility] at midpoint is a thousand metres or thereabouts and it?s rolling through to the south and thickening. It won?t be long before it will be a bit worse at the threshold at 34L?. The crew of QPC did not hear that information as they using a different radio frequency, but ATC advised them at 0615 that ?? the fog is now moving around at the airfield. I can?t guarantee you the same visibility as [the] company 747 of yours [that] landed on 34L?. Soon after, at 0617, one minute before the nominated divert time, ATC advised the crew of QPC that the RVR for runway 34L from the threshold was 2,000 m, which was 500 m more than the landing minima.

At 0622, the aircraft was established on the ILS approach for runway 34L. At about the same time, the crew of a preceding aircraft on approach to runway 34L conducted a missed approach because they were unable to see the runway lights. The controller passed that information to the crew of QPC. During the approach, the pilot in command of QPC saw the threshold of the adjacent parallel runway 34R and he advised ATC that he would need a right orbit onto the ILS of the adjacent runway to enable a landing. However, soon after, he decided to continue the approach to runway 34L as the aircraft was configured for an autoland. The pilot in command reported that he was concerned that if a missed approach was conducted and the aircraft was then manoeuvred for an approach to the adjacent parallel runway 34R, the heavy fog to the north may have moved across that runway during the next approach.

The aircraft was certified for autoland operations using the auto-flight system to control the aircraft during the approach and landing phase, and the crew had undergone the required training to conduct an autoland. The instrument landing systems for the various runways at Sydney were only certified to facility performance category one criteria, which meant that pilots were not permitted to continue approaches, including autolands, to runway 34L when the weather conditions were less than the specified category one landing minima.

The crew conducted a runway 34L ILS approach using the aircraft?s autoland capability and landed at 0625 in weather conditions that were less than the specified landing minima.

Civil Aviation Regulation (CAR) 257(5) specified that ?? if an emergency arises that, in the interests of safety, makes it necessary for an aircraft to land at an aerodrome where the meteorological minima is less than that determined for that aircraft operation at that aerodrome? then CAR 257(4) did not apply. CAR 257(4) stipulated that if an element of the meteorological minima for the landing of an aircraft at an aerodrome was less than that determined for the aircraft operation at the aerodrome, the aircraft was not to land at that aerodrome.

Availability and selection of alternate aerodromes

The aircraft operator provided information about aerodromes approved for A330 operations in the Route Manual Supplement (RMS), which was carried onboard the aircraft for flight crew use. If an aerodrome was approved for normal operations and the weather conditions were forecast to be better than the alternate minima, the aerodrome was classified as ?suitable aerodrome? and could be used as an alternate aerodrome for the destination. Brisbane, Coolangatta, Melbourne and Adelaide were the closest aerodromes that could be used as ?suitable aerodromes? for operations to Sydney.

The RMS also listed other aerodromes that were categorised as either emergency or adequate aerodromes that could be used during non-normal operations. Emergency aerodromes had runways of a sufficient length that could be used by A330 aircraft in an emergency situation. Nowra and Canberra were the closest emergency aerodromes to Sydney.

Adequate aerodromes met the requirements detailed in Civil Aviation Order 82.0, Appendix 2. If the weather conditions were forecast to be better than the specified ?adequate criteria?, an adequate aerodrome was considered to be a ?usable adequate aerodrome? and could be used by A330 aircraft following a critical system failure. The closest adequate aerodromes to Sydney were Williamtown and Richmond.

During the latter phase of the occurrence flight, the closest ?suitable aerodrome? was Melbourne and, once the aircraft flew past the DPA at 0518, the fuel on board was insufficient for a diversion to that aerodrome. When the crew became aware of the presence of fog near Sydney at about 0540, they obtained information about two adequate aerodromes, Williamtown and Richmond, and an emergency aerodrome, Canberra (see Sequence of events for the crew?s assessment of the weather conditions at these aerodromes).

The pilot in command stated that he considered that ATC had to be advised of an emergency condition in order to use an emergency aerodrome listed in the RMS. The operator also advised that the decision to divert to Canberra would have required the broadcast of PAN.

Aircraft fuel load

The aircraft departed Perth with 28,900 kg of fuel, which was 2,500 kg more than the minimum amount required by the operator?s approved fuel policy for the flight. The planned flight time from Perth to Sydney was 210 minutes and the fuel load gave the aircraft an endurance of approximately 315 minutes. As noted earlier, the aerodrome forecast did not require additional fuel, for either holding or a diversion, to be carried on this flight to Sydney.

The operator?s Flight Administration Manual (FAM) contained the fuel policy that specified the minimum mandatory fuel requirements approved by the operator for the operation of its aircraft. The FAM stated ?? it is recognised that there are occasions when a flight may pass DPA with the required fuel on board and a subsequent deterioration in forecast weather may then result in the minimum mandatory requirements ? not being met?.

After the occurrence, the operator calculated that the total amount of fuel required to divert the aircraft from a missed approach at Sydney to a landing at Canberra with reserves intact was 6,700 kg. Information from the aircraft?s flight data recorder showed that the aircraft landed at Sydney with about 6,900 kg of fuel remaining.

Meteorological information

The Bureau of Meteorology advised that fog at Sydney aerodrome was difficult to forecast as it was an uncommon event with between four and eight occurrences per year. Although the fog forecasting models had been upgraded in 1999, those models did not predict the formation of fog on the date of the occurrence. The classic fog scenario occurs when radiative cooling in the north-west area of the Sydney basin produces fog, which then moves to the aerodrome in a north-westerly surface airflow. For this airflow to form, several hours of clear sky is required to produce enough cooling so that the surface airflow uncouples from the gradient level airflow, which is 2,000 ft to 3,000 ft above ground level and may be moving in a different direction.

As the cloud was expected to persist during the morning of the occurrence, the duty operational meteorologist considered that the airflow uncoupling would not occur and the surface airflow would remain the same as the gradient airflow, which was from an east to north-easterly direction. At 0230, the high resolution computer forecasting models indicated precipitation and an east to north-east surface airflow. Although fog had formed in some western areas of the Sydney basin by 0330, the meteorologist considered that the rain showers near Sydney aerodrome would assist in mixing the slightly stronger east to north-easterly gradient airflow down to the surface airflow and hence reduce the risk of fog drifting in from the north-west.

The low-level cloud at the aerodrome cleared at about 0500, which coincided with the surface airflow tending to be from the north-west. About 40 minutes later fog was observed to the north-west of the aerodrome and soon after it started to move over the runways. The deterioration in visibility associated with the movement of the fog was rapid. A reduction in visibility from 2,000 m to 400 m was reported during an 11 minute period from 0552 to 0603. The fog did not clear until 0830.

The Canberra 0530 special aerodrome weather report (SPECI) obtained by the crew indicated that the wind was from the south at 3 to 4 kts, visibility was greater than 10 km, with 7 oktas of cloud at 2,100 ft above the aerodrome. The Canberra 0600 TTF was not obtained by the crew, but it did not vary significantly from the 0530 SPECI. According to the applicable Jeppesen Airport Chart, Canberra was available as an alternate aerodrome provided the cloud base above the aerodrome was not below 2,084 ft (2,144 ft for runway 17) and the visibility was not less than 6 km (7 km for runway 17). That minima was applicable with an actual QNH, which was available at Canberra, and was being broadcast on 116.7 MHz.

Provision of weather information to the flight crew

Airservices Australia (Airservices) was the air traffic service (ATS) provider. The procedures for the provision of weather information to flight crew by air traffic controllers were detailed by Airservices in the Manual of Air Traffic Services (MATS). The Aeronautical Information Publication (AIP), also published by Airservices, was an Australian operational document used by pilots. The information in the AIP that related to the provision of weather information was in accordance with the MATS.

The MATS required air traffic controllers to monitor and assess information from various reports. These included weather forecasts, amended weather forecasts and observations and reports that indicated the weather conditions at the destination aerodrome had deteriorated below the alternate minima. If that information was assessed to be of ?an unexpected and critical nature?, controllers were required to broadcast a hazard alert to flight crews.

At 0554, soon after the fog was observed moving over the aerodrome, the controllers amended the ATIS to include a hazard alert due to unforecast fog. The ATIS also advised pilots to expect an ILS approach to either runway 34L or 34R and that the RVR had reduced to 800 m in fog. This information was also broadcast at that time by the controller handling QPC.

A special aerodrome weather report (SPECI) was issued at 0603, and this report indicated that the visibility had reduced to 400 m in fog, which was below the landing minima of any runway at Sydney. The TTF appended to the SPECI indicated that these conditions would continue until 0800. The 0603 SPECI information was not passed to the crew of QPC. However, they became aware of the deterioration in the weather conditions at 0611 when ATC provided information about the RVR on runway 16R.

The RVR was assessed by approved observers in motor vehicles positioned near the runway thresholds. To determine the RVR, the observers counted the number of visible runway lights or identifiable features adjacent to the runway. This information was then broadcast to the aerodrome controller in the control tower. During the occurrence, there were observers in vehicles located near the thresholds of runways 16R, 34L and 34R.

Landing information, including RVR, was provided to flight crews either by controllers, or by the crews listening to the ATIS broadcast. The MATS section 5.1.11 contained instructions regarding the format of weather information provided in the ATIS. The MATS specified that, when the visibility was between 1,500 m and 800 m, the ATIS may report RVR information. It also stated that when visibility was 800 m or less, the RVR ?shall be reported? in the ATIS broadcast. The MATS and the AIP did not specify that the RVR information in an ATIS broadcast was to be for the touchdown zone of the runway in use.

When the ATIS was amended at 0554 to include the 800 m RVR information, the actual visibility at the touchdown zone of runway 34L was greater than that figure.

The ICAO Annex 3 ? Meteorological Service for International Air Navigation (Annex 3), contained the standards and recommended practices regarding the provision of metrological services in the aviation sector. Paragraph 4.7.4 of Annex 3 recommended that RVR observations should be made on precision approach runways for category one instrument approach and landing operations. Runway 16R and 34L at Sydney were category one precision approach instrument runways. ICAO Annex 14 ? Aerodromes defined a category one runway as ?? an instrument runway served by ILS ? and visual aids intended for operations with a decision height not lower than 60 m (200 ft) and either a visibility not less than 800 m or a runway visual range not less than 550 m?. Paragraph 4.7.2 of Annex 3 required that:

Runway visual range observations shall be representative of the touchdown zone and, depending on the category of operation for which the runway is intended and the length of the runway, of the mid-point and stop-end of the runway.

Following the amendment of the Sydney ATIS at 0554, the weather conditions continued to deteriorate with the visibility reducing to 400 m by about 0600. However, the next amendment of the ATIS was not until 0633. Requirements for the revision of ATIS information were covered in the MATS section 5.1.12. Paragraph 5.1.12.1 specified that when the current value of the visibility information was less than 1,500 m, controllers were to amend the ATIS as required if the value of the visibility was expected to vary and remain that way for at least 15 minutes.

Paragraph 5.1.12.2 of the MATS stated that in situations where controller workload precluded the amendment of the ATIS in accordance with the MATS requirements:

Tower controllers shall ensure that aircraft under their control are advised of sudden and perhaps unexpected changes to the aerodrome information, pending an amended ATIS.

Notwithstanding these requirements, there was no provision in the MATS for controllers, who were located remote from the control tower and who were passing ATIS information to flight crews, to be made aware of changes to the aerodrome information pending the updating and broadcasting of an amended ATIS.

1 The landing minima are the Civil Aviation Safety Authority (CASA) specified meteorological conditions of cloud ceiling and visibility. In order for an aircraft to land at an aerodrome, the actual weather conditions need to be at or above the landing minima.
2 Okta is a meteorological unit, equal to the area of one eighth of the sky.
3 Alternate minima are the cloud base and visibility values specified by CASA for a particular aerodrome such that, if the conditions are forecast to be worse than the alternate minima, the pilot in command must provide for a suitable alternate aerodrome.
4 The term DPA was used by the operator to indicate the point along the flight plan track that equated to the last position furtherest removed from the departure aerodrome from which an aircraft could divert to a nominated off-track alternate aerodrome. The minimum fuel required to be onboard at the DPA comprised the flight fuel to the alternate aerodrome, a variable fuel reserve, approach fuel, a fixed fuel reserve and holding fuel (if required).
5 The International Civil Aviation Organization (ICAO) Annex 3 - Meteorological Service for International Air Navigation defined runway visual range as '? the range over which the pilot of an aircraft on the centre line of a runway can see the runway surface markings or the lights delineating the runway or identifying its centre line'.
6 PAN is an expression, spoken three times in succession, used in the case of an urgency condition. ICAO Annex 10 - Aeronautical Telecommunications, Volume II, defined an urgency condition as '? a condition concerning the safety of an aircraft or other vehicle, or of some person on board or within sight, but which does not require immediate assistance'.

Occurrence summary

Investigation number 200401270
Occurrence date 06/04/2004
Location Sydney, Aero.
State New South Wales
Report release date 02/08/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Fuel - Other
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Airbus
Model A330
Registration VH-QPC
Sector Jet
Operation type Air Transport High Capacity
Departure point Perth, WA
Destination Sydney, NSW
Damage Nil

British Aerospace Plc 3201, VH-OAE

Safety Action

Safety Action

Following this and the other recent post SB A72-2087 bull gear failures, the following safety actions have been taken:

Engine Manufacturer

The manufacturer has re-assessed the SOAP procedures in Alert SB TPE 331-A79-0034 and has provided additional training to their team reviewing that data, to ensure that the guidelines are properly understood and more conservatively applied.

In August 2004, the manufacturer released Alert SB, SB TPE 331-A72-21146. That SB was a warning to operators and stated:

WARNING:

FAILURE TO COMPLY WITH THIS SERVICE BULLETIN COULD RESULT IN DISTRESS OF THE BULL GEAR, THE HIGH SPEED PINION TORQUE SHAFT, OR THE HIGH SPEED PINION COUPLER. IF LEFT UNCORRECTED, THIS DISTRESS COULD RESULT IN EITHER ENGINE SURGE OR OVERSPEED, OR COULD RESULT IN AN IN-FLIGHT SHUTDOWN. ADDITIONALLY, FRAGMENTS OF THE BULL GEAR COULD EXIT THE GEARBOX AND BE STRUCK BY THE PROPELLER. ON RIGHT HAND ENGINE INSTALLATIONS, THESE FRAG¬MENTS MAY BE REDIRECTED AGAINST THE AIRCRAFT FUSELAGE WITH SUFFICIENT FORCE TO CAUSE FUSELAGE PENETRATION AND COULD RESULT IN SERIOUS INJURY OR DEATH TO PERSONNEL AND POSSIBLE LOSS OF THE AIRCRAFT.

The SB provided the authorisation and instructions for the rework and or replacement of the Intermediate Housing and Gear (Diaphragm) Assembly part number 3102593-7, with assembly part numbers 3102593-12 or 3107191-4. Those housings contain newly designed helical pinion and bull gears, pinion gear bearings, torque shaft assembly and lubrication components. Helical gear teeth lie along a helix at an angle to the shaft7. The SB also stressed that priority be given to incorporation of the bulletin on an engine positioned on the right of an aircraft, due to the possibility of gearbox debris striking the fuselage in the event of a failure.

Civil Aviation Safety Authority

In December 2004, CASA issued Airworthiness Directive (AD) AD/TPE 331/628. That AD superseded AD/TPE 331/55 Amdt 3, 57 Amdt 1 and 58 Amdt 2. The CASA AD/TPE 331/62 incorporated the requirements of SB TPE331-A79-0034, SB TPE 331-A72-2087 and the associated Rework SB's, with the requirements of SB TPE 331-A72-2114.
The background statement for the AD indicated, in part:

This directive provides an alternative to mandatory requirements by approving the use of the manufacturer's referenced service bulletins as an alternative to both compliance times given and the requirement to replace certain parts with other parts for certain model engines. The fitment of the new designed parts will provide terminating action for the repetitive inspections detailed in this Directive.

Operator

As a result of an internal investigation into this occurrence, that involved contact with other operators in Europe and the United States who have experienced similar failures, the operator instigated a seating allocation limitation in their Jetstream aircraft. That limitation was highlighted to crews by a safety memorandum and by a company standardisation directive, dated 1 December 2004.
The memorandum stated the following:

In response to a recent service bulletin from Honeywell, seats [in] Row 1 on BAe32 [Jetstream] aircraft are only to be occupied under the following circumstances:

• Where the number of passengers is 16 or more and the seat is required for a passenger.
• Where there is an operational requirement for operational personnel to occupy a seat in Row 1 such as training and checking or auditing.
• Where directed by the captain (such as a surveillance flight by a CASA Safety Auditor).

This measure will further reduce the risks associated with potential bull gear failure on the TPE 331 [engined] aircraft.

6. Honeywell Service Bulletin - TPE 331-A72-2114 - ENGINE - REDUCTION GEAR AND SHAFT SECTION - REPLACE GEARSHAFT (SUN AND BULL GEAR) ASSEMBLY, PART NO. 3107037-9/-10, 3107122-1, 3107162-1, 3108222-1, OR 3108294-1 WITH PART NO. 3108384-1, issued 20 Aug 04.

7.ASM International, Materials Information Society Handbook, Volume II.

8. AD/TPE 331/62 has been amended to AD/TPE 331/62 Amdt 1, effective from 4 August 2005. This amendment includes provision for an alternative means of compliance for TPE 331 engines fitted to CASA 212 aeroplanes. There has been no other change to the AD. At the time of drafting the original AD the [engine] manufacturer had not provided CASA with documents detailing the AMOC [Alternative Means of Compliance].

Analysis

Analysis

The investigation determined that the bull gear failed as a result of a previously known high cycle fatigue cracking mechanism.

The Civil Aviation Safety Authority Airworthiness Directive (AD) requiring compliance with the manufacturer's Service Bulletin (SB) A72-2087 had been completed on the engine. However, the bull gear failed at less than half of the manufacturer's projected component life.

The diaphragm housing had been extensively damaged following the release of the section of the bull gear rim. That damage had prevented the investigation determining the housing's pre-failure condition and whether its condition had contributed to the failure.

At the time of the failure, the spectrometric oil and filter analysis program (SOAP) analysis had been carried out and assessed in accordance with the manufacturer's procedures. While the filter weight increases noted in the engine on 3 February 2004 and 1 April 2004 were within the manufacturer's 'normal sample' range, the above average filter weight, coupled with the traces of carbon steel may have been an indicator of the impending bull gear failure.

The crew handled the engine failure appropriately in accordance with the operator's procedures. The report of smoke in the cabin of the aircraft during the failure was consistent with the ingestion of engine oil into the compressor assembly immediately following the uncontained failure.

Factual Information

Factual Information

At 1100 Central Standard Time on 16 April 2004, a British Aerospace Plc, J32, Jetstream aircraft registered VH-OAE, with 2 pilots and 19 passengers on board, was on descent, during a scheduled passenger flight from Melbourne, Victoria to Mount Gambier, South Australia. As the aircraft passed through flight level (FL) 140, approximately 37 NM from Mt Gambier, the crew reported hearing a bang from the right engine. Simultaneously, the aircraft yawed to the right and they heard something impact the right side of the fuselage. Some smoke was evident in the cockpit.

A check of the aircraft's engine instruments confirmed a problem with the right engine and the crew shut down the engine and feathered the right propeller in accordance with the operator's quick reference handbook drills. The crew then advised air traffic control of the situation and continued for a landing at Mount Gambier Airport.

An inspection of the aircraft by the operator revealed that there had been an uncontained failure of the propeller reduction gearbox on the right TPE 331-12UHR-702H turboprop engine, serial number P66338C. There was also evidence of impact damage on the right side of the fuselage, below the co-pilot's side window area. That impact had not breached the aircraft's pressure hull.

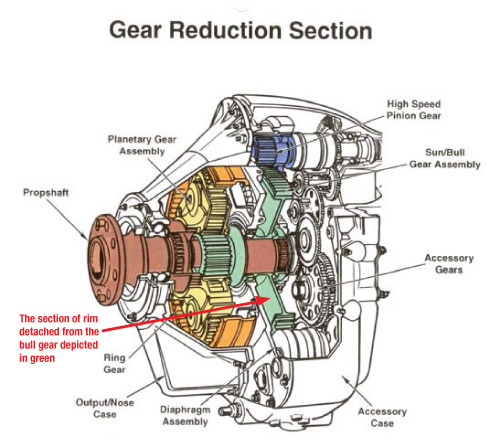
An examination of the engine, supervised by the Australian Transport Safety Bureau (ATSB), found that a section of the spur gear teeth from the outer rim of the reduction gearbox bull gear, had detached during engine operation (See Figure 1). Spur gear teeth are radial, uniformly spaced around the gear's outer periphery and parallel to the shaft axis1. The detached section of gear had penetrated the diaphragm housing (intermediate gearbox housing) and the gearbox accessory case, before exiting the engine through the compressor air intake.

Figure 1: Cutaway diagram of TPE 331 reduction gearbox

aair200401353_001.jpg


The hole in the accessory case had allowed engine oil to escape and flow over the engine cowling, with metallic debris and oil entering the engine's compressor intake. Once inside the compressor, the oil was able to enter the aircraft's compressor bleed air system that supplied the aircraft's air conditioning and pressurisation air. There was also significant associated damage to the diaphragm housing, the high speed pinion and compressor/turbine main shaft, with metallisation2 observed on the turbine and exhaust sections.

An ATSB Technical Analysis report (Appendix A), on the mode of failure of the bull gear, part number 3108295-1, found that the gear had failed as a result of a mechanism known to the manufacturer. The report indicated that the progressive propagation of high cycle fatigue cracking within the gear web and rim transition region, had caused a section of the gear rim to separate from the gear.

The engine manufacturer had introduced several changes to the bull gear design to address 'reliability and reparability issues' that had occurred in the TPE 331 engine type. Among those were changes in gear relief, gear tooth roots had been ground and shot peened to improve fatigue life, the gear rim inside diameter was shot peened to increase fatigue resistance and a coating was added to the gear web to dampen gear vibrations. The engine manufacturer reported that despite those actions some of the re-worked and coated gears had a higher failure rate than non-reworked gears.

The engine manufacturer also investigated TPE 331 engine diaphragm housings, in which gears had failed, to ascertain if distortion of the housing could cause bull gear to pinion gear misalignment. Several problems were identified with those housings that may have contributed to the gear failures. These included bull gear to pinion gear centreline growth and misalignment, growth between diaphragm to gearbox alignment pins and out-of-round bearing bores.

In October 2001, the engine manufacturer issued Service Bulletin (SB) A72-20873 in response to 16 in-service bull gear rim separations and 13 high speed pinion torque shaft failures. Four of those failures resulted in gearbox debris being ejected from the engine. One failure resulted in the penetration of the right side of an aircraft's pressure hull by a gear fragment. The bulletin indicated that high tooth loading on the bull gear to high speed pinion mesh, bull gear tooth profile, and distortion of the intermediate gearbox housings, had resulted in abnormal wear and subsequent failure of the assemblies.

Service Bulletin A72-2087 required replacement of the bull gear and high speed pinion with new, zero-time components, at intervals not to exceed 3,600 hours in service. It also required the inspection and the rework/overhaul of some gearbox components such as the diaphragm housing, plus a more stringent periodic inspection of specified gearbox components to ensure an optimum operating environment for the bull gear. At the time of failure, the bull gear assembly in this engine had accrued 1,199.55 hours and 1,523 cycles since installation. The engine had accrued a total of 10,755.7 hours and 12,295 cycles since new.

In Australia, the Civil Aviation Safety Authority (CASA) issued Airworthiness Directive (AD) AD/TPE 331/57 to require compliance with SB A72-2087. That AD became effective on 31 October 2001. Amendment 1 to that AD was issued in January 2002. The AD actions had been incorporated into the occurrence engine at the manufacturer's German maintenance facility on 20 December 2002.

Information received from the engine manufacturer following this occurrence, indicated that there had been three bull gear failures in post SB A72-2087 engines. One of those failures was the subject of a UK Air Accidents Investigation Branch (AAIB) investigation, published in AAIB Bulletin number 7/2005. Information from the AAIB on that failure indicated that the bull gear had failed in a similar manner to the gear in this occurrence.

The engine manufacturer reported that a spectrometric oil and filter analysis program (SOAP)4 was used to monitor an engine's in-service condition and to reduce the possibility of a premature mechanical failure. That program monitored the type and quantity of the deposits in the engine oil and oil filters over a specified period. A trending feature within that program could highlight an engine with a rapidly increasing filter 'weight' and indicate that further maintenance action was required. A high filter weight quantity of Carbon Steel in a sample could indicate a problem with the bull gear assembly. In November 2000, the engine manufacturer issued Alert Service Bulletin TPE 331-A79-00345 that changed the SOAP interval periodicity to a fixed 100+/- 20 engine hours to minimise variability. On 25 January 2001, CASA issued AD/TPE 331/55 that required Australian compliance with that Alert SB.

The operator had complied with the engine manufacturer's and CASA's SOAP requirements, forwarding samples to the manufacturer's approved venue for testing. The operator reported that they had become concerned about a SOAP report for the occurrence engine that had been received on 3 February 2004. That report, although still within the manufacturer's 'normal sample' guidelines, had a significantly higher filter weight result than had been previously noted for the engine. When queried, the manufacturer confirmed the results of the sample and indicated that a higher reading may be seen following an engine oil change. The engine oil had been changed 101 engine hours prior to that sample being taken. In the subsequent SOAP sample taken 60 engine hours later, on 24 February 2004, the filter weight had returned to a similar level to that of the pre-3 February 2004 samples. The final sample taken prior to the occurrence, on 1 April 2004, was higher than usual and all of the samples had traces of carbon steel.

1. ASM International, Materials Information Society Handbook, Volume II.

2. Metal pulverised by the compressor becomes molten or burned in the combustion chamber and flows rearward, attaching to the turbine and exhaust assemblies (US Department of the Air Force.(1987). Safety Investigative Techniques (AF Pamphlet 127-1, Volume II). Washington DC: Author).

3. Honeywell Alert Service Bulletin - TPE 331-A72-2087, ENGINE - REDUCTION GEAR AND SHAFT SECTION - Replace Gearshaft (Sun and Bull Gear) Assembly, Part No. 3107037-9/10, 3107122-1, 3107162-1, or 3108222-1, or 3108294-1 with Part No. 3108294-1, issued October 2001 and revised 16 November 2001.

4.Service Information Letter - P331-97 - THE HONEYWELL SPECTROMETRIC OIL AND FILTER ANALYSIS PROGRAM FOR ALL TPE 331 ENGINES EXCEPT -14GR/HR ENGINES; Revision 10, Apr 5/02.

5. Honeywell Alert Service Bulletin - TPE 331-A79-0034 - OIL DISTRIBUTION - DECREASED TIME INTERVAL BETWEEN SPECTROMETRIC OIL (AND FILTER) ANALYSIS PROGRAM (SOAP) SAMPLING; Revision 4, Apr 5/02.

Summary

At 1100 Central Standard Time on 16 April 2004, a British Aerospace Plc, J32, Jetstream aircraft registered VH-OAE, with 2 pilots and 19 passengers on board, was on descent, during a scheduled passenger flight from Melbourne, Victoria to Mount Gambier, South Australia. As the aircraft passed through flight level (FL) 140, approximately 37 NM from Mt Gambier, the crew reported hearing a bang from the right engine. Simultaneously, the aircraft yawed to the right and they heard something impact the right side of the fuselage. Some smoke was evident in the cockpit.

Occurrence summary

Investigation number 200401353
Occurrence date 16/04/2004
Location 65 km E Mount Gambier, (VOR)
Report release date 20/01/2006
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Propeller/rotor malfunction
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer British Aerospace
Model 3200
Registration VH-OAE
Serial number 851
Sector Turboprop
Operation type Air Transport Low Capacity
Damage Nil

Fumes, Boeing 747-400, 9M-MPE, Ceduna, South Australia, on 20 April 2004

Factual Information

The Boeing 747-400 aircraft, registered 9M-MPE, was conducting an international scheduled passenger flight from Kuala Lumpur, Malaysia to Melbourne. During cruise at flight level 390, the cabin crew reported an electrical smell near doors 1, 2 and 4. The flight crew immediately completed the "Smoke, Fumes, Fire, Electrical" checklist actions and the smell dissipated. Approximately one hour later, a similar smell became evident in the cockpit and the flight crew elected to divert the aircraft to Adelaide as a precaution.

After landing at Adelaide, an engineering inspection of the aircraft was conducted by the operator's engineers. This inspection revealed that the air conditioning right overhead recirculation fan had seized and the left overhead recirculation fan was causing the circuit breaker to trip. Both overhead recirculation fans were isolated electrically in accordance with the requirements of the aircraft's Minimum Equipment List and the aircraft was returned to service.

Summary

The Boeing 747-400 aircraft, registered 9M-MPE, was conducting an international scheduled passenger flight from Kuala Lumpur, Malaysia to Melbourne. During cruise at flight level 390, the cabin crew reported an electrical smell near doors 1, 2 and 4. The flight crew immediately completed the "Smoke, Fumes, Fire, Electrical" checklist actions and the smell dissipated. Approximately one hour later, a similar smell became evident in the cockpit and the flight crew elected to divert the aircraft to Adelaide as a precaution.

After landing at Adelaide, an engineering inspection of the aircraft was conducted by the operator's engineers. This inspection revealed that the air conditioning right overhead recirculation fan had seized and the left overhead recirculation fan was causing the circuit breaker to trip. Both overhead recirculation fans were isolated electrically in accordance with the requirements of the aircraft's Minimum Equipment List and the aircraft was returned to service.

Occurrence summary

Investigation number 200401390
Occurrence date 20/04/2004
Location Ceduna
State South Australia
Report release date 10/05/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Fumes
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 747
Registration 9M-MPE
Sector Jet
Operation type Air Transport High Capacity
Departure point Kuala Lumpur, MALAYSIA
Destination Melbourne, VIC
Damage Nil

Beech Aircraft Corp B200, VH-FDG

Summary

The Australian Transport Safety Bureau did not conduct an on-scene investigation of this occurrence. The report presented below was prepared principally from information supplied to the Bureau.

REPORTED INFORMATION

At 0337 Western Standard Time on 11 April 2004, a Beech Aircraft Company Super King Air aircraft, registered VH-FDG, with one pilot, a flight nurse and one passenger on board was conducting an aeromedical flight from Paraburdoo to Albany WA. The pilot reported that, during cruise at flight level 310, the right engine surged, followed by rising Inter-Turbine Temperature. The engine was shut down and the flight diverted to Jandakot, WA.

A subsequent engineering examination by the operator's maintenance engineers revealed that the engine had been subjected to severe over-temperature damage resulting in turbine failure.

The engine was sent to the manufacturer's overhaul facility for further examination. The examination confirmed that the reported damage resulted from over-temperature conditions in the engine. The engine's fuel control unit (FCU) was removed and tested to determine if it conformed to the required fuel scheduling specifications. The testing revealed that the FCU was not metering the fuel to the appropriate schedule and that the engine may have been subject to hot starting1 conditions and a rich acceleration2 schedule. These conditions would have shortened the service life of the engine, leading to the reported failure.

1 Hot starting refers to a higher than normal temperature reached during the engine starting cycle.
2 A rich acceleration schedule indicates that that FCU was providing a higher than normal fuel flow to the engine during starting.

Occurrence summary

Investigation number 200401549
Occurrence date 11/04/2004
Location 74 km S Mount Magnet, (NDB)
State Western Australia
Report release date 14/04/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Abnormal engine indications
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Beech Aircraft Corp
Model 200
Registration VH-FDG
Serial number BB-1172
Sector Turboprop
Operation type Aerial Work
Departure point Paraburdoo, WA
Destination Albany, WA
Damage Nil

Bell 47G-3B1, VH-UTY

Safety Action

Because of possible fleet-wide safety implications, the Australian Transport Safety Bureau advised the Civil Aviation Safety Authority (CASA) of its preliminary factual findings regarding the incorrect fitment of the tail rotor control pedals.

CASA conducted an immediate survey of operators of this helicopter type and requested an immediate inspection by all operators for compliance with AD/Bell 47/69. At least two other operators at that time reported that they had Bell 47 helicopters with tail rotor control pedals that did not comply with the AD. As a result, CASA issued AD/Bell 47/69 Amdt 1, that became effective on 30 September 2004, requiring all variants of the Bell Helicopter 47 series to be inspected for compliance within 10 hours after the effective date of the directive and every 12 months thereafter.

Factual Information

At approximately 1211 Eastern Standard Time on 2 April 2004, the pilot of a Bell Helicopter Company 47G Soloy helicopter, registered VH-UTY, was conducting fire-ant baiting operations at Nudgee, about 5 km north-west of Brisbane Airport. The operator's chief pilot occupied the right control position and was supervising the pilot.

Near the end of a baiting run, the chief pilot told the pilot that he wanted to demonstrate a procedural turn and asked the pilot to follow him through the manoeuvre. Both pilots reported that, during the turn, the helicopter began to yaw right. The chief pilot then said that he was taking control of the helicopter. He reduced engine power but was unable to arrest the right yaw. The helicopter continued to descend towards a canal and struck the water slightly nose down and banked to the right. Both occupants were injured in the impact but were able to exit from the helicopter unaided.

The pilot reported that he had completed two previous baiting operations in the helicopter during that day without incident.

A subsequent examination of the helicopter found that the tail rotor control pedals installed at the right control position operated in the reverse sense, compared with the tail rotor control pedals installed at the left control position. That meant that tail rotor control pedal inputs made by the chief pilot would have produced a yaw response opposite to that which would normally be expected.

The helicopter operator reported that the tail rotor control pedals for the right control position had been refitted to the helicopter before the accident flight.

In 1954, the Bell Aircraft Corporation, as it was then known, issued Service Bulletin (SB) 98. The SB required installation of a stop assembly (part number 47-722-165-1), under both control position footrests. The purpose of the stop assembly was to prevent the incorrect re-installation of the tail rotor control pedals. UTY was manufactured in 1966, and the stop assembly would have been incorporated as a standard build item during manufacture.

In October 1971, the then Australian Department of Civil Aviation issued Airworthiness Directive (AD) AD/Bell47/69 titled Tail Rotor Control Pedal Assembly Interference Bracket. That AD, which mandated the installation of the interference (stop) brackets to all Bell 47G series helicopters as introduced by Bell SB 98, was still current at the time of the accident.

Examination of the helicopter showed that only part of the tail rotor control pedal assembly bracket as specified in AD/Bell 47/69, remained fitted in the helicopter. The majority of the bracket had previously been removed. There was no evidence to indicate that the removal was as a result of wear or damage sustained in the accident. The maintenance organisation that certified for the last scheduled maintenance check advised that the bracket was in place, and that the co-pilot tail rotor control pedals were not fitted at that time.

The helicopter's maintenance documentation contained no record of the installation of the right tail rotor control pedals, or of the required independent inspection of the flight controls after the installation of the tail rotor control pedals.

The helicopter examination also found that the forward section of the tail rotor drive output shaft, from the main gearbox to just forward of the first bearing hanger assembly, had separated. The separated section was not found. Examination of the remaining broken section of the drive shaft indicated that it had separated due to overload forces that occurred during the accident impact sequence. There was no evidence found of any pre-existing fault in the shaft.

Summary

At approximately 1211 Eastern Standard Time on 2 April 2004, the pilot of a Bell Helicopter Company 47G Soloy helicopter, registered VH-UTY, was conducting fire-ant baiting operations at Nudgee, about 5 km north-west of Brisbane Airport. The operator’s chief pilot occupied the right control position and was supervising the pilot.

Occurrence summary

Investigation number 200401217
Occurrence date 02/04/2004
Location 5 km NW Brisbane, Aerodrome
State Queensland
Report release date 26/10/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Loss of control
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Bell Helicopter Co
Model 47
Registration VH-UTY
Serial number 6548
Sector Helicopter
Operation type Aerial Work
Departure point Brisbane QLD
Destination Brisbane QLD
Damage Substantial

Robinson R22 Beta, VH-HHD, 56 km north-north-west of Charters Towers, (ALA), Queensland, on 3 May 2004

Summary

On 31 March 2004, at 0600 Eastern Standard Time, the Robinson R22 helicopter with one pilot on board departed on a ferry flight to commence mustering operation from a property approximately 15 minutes flying time to the north-north-east. The pilot reported that he landed at the property and picked up a passenger who was going to show him the paddocks, fences and laneways.

At about 1000, after mustering cattle into a small paddock, the pilot made an approach to land beside a fence. The pilot indicated that the weather was fine with good visibility. The wind was from an easterly direction at 5 kts and the temperature was 25 degrees C. He reported that he saw a powerline and aimed to land adjacent to a point where the powerline changed direction. However, he did not see a third wire, which the helicopter struck at a height of about 30 ft. The helicopter spun into the ground and landed on a barbed wire fence. The helicopter sustained substantial damage to the tail boom, lower vertical fin and tail rotor blades. The two occupants escaped with minor injuries.

Occurrence summary

Investigation number 200401181
Occurrence date 31/03/2004
Location 56 km NNW Charters Towers, (ALA)
State Queensland
Report release date 03/05/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Minor

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22
Registration VH-HHD
Serial number 3022
Sector Helicopter
Operation type Aerial Work
Departure point Haven Glen, QLD
Destination Eumara Springs Station, QLD
Damage Substantial

Boeing 767-338ER, VH-OGB

Safety Action

In addition to the previous safety actions reported by the ATSB in occurrence report number 200402411, the operator of OGB has implemented the following procedures to be followed when its aircraft are operating in the Ujung Pandang FIR:

Offset tracks are to be flown during en-route phase of flight in all (radar and non-radar) airspace

Aircraft are to return to on track by the Indonesian FIR boundaries and for climb from, and descent to, airports.

Summary

On 22 March 2004, at about 0435 Coordinated Universal Time (UTC), a Boeing Company 767-338ER, registered VH-OGB, and a Boeing Company 767-319, registered ZK-NCF, were involved in a serious incident in the Ujung Pandang Flight Information Region (FIR).

OGB was southbound and NCF was northbound on air route B473, between waypoint OLENG and waypoint OPABA. The crew of OGB advised Ujung Control that they were at OLENG at 0423 and were level at flight level (FL) 350. The crew later reported that they requested approval from Ujung Control to climb their aircraft to FL370. Ujung Control subsequently approved that request. During that climb, and passing approximately FL355, the crew of OGB received a traffic advisory on their aircraft's traffic alert and collision avoidance system (TCAS), followed by a resolution advisory, about NCF. The resolution advisory instructed the crew of OGB to descend their aircraft. The crew complied with the resolution advisory and descended their aircraft to FL350. The crew later reported that, during the descent manoeuvre, they saw NCF pass 600 ft above their aircraft.

NCF was northbound on air route B473, between waypoint OLENG and waypoint OPABA and was level at FL360. The crew later reported that they received a TCAS resolution advisory on OGB, travelling in the opposite direction. The crew of NCF climbed their aircraft in response to the resolution advisory. The crew later reported that they observed OGB on their TCAS, pass 400 ft below them.

The Australian Transport Safety Bureau (ATSB) was advised of the serious incident and commenced an investigation. The crew of OGB was interviewed and data from that aircraft's quick access recorder was analysed. As the incident occurred within Indonesian territory, the Indonesian National Transportation Safety Committee (NTSC) had the responsibility to conduct an investigation in accordance with Annex 13 to the Convention on International Civil Aviation.

On 26 March 2004, the NTSC informed the ATSB that they had commenced an investigation into the incident and the ATSB appointed an accredited representative to that investigation. The NTSC, being the investigation agency of the country in which the incident occurred, will be preparing the report and has control over the public release of any investigation findings.

As a result of another occurrence within an Indonesian FIR, which involved aircraft from the same Australian operator, that operator implemented new procedures to be followed when its aircraft are operating in Indonesian FIRs (see ATSB occurrence report number 200402411).

The Bureau will publish the NTSC report, when released by the NTSC, on the ATSB website.

Occurrence summary

Investigation number 200401115
Occurrence date 22/03/2004
Location 130 km S Oleng, (IFR)
State International
Report release date 14/03/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Loss of separation
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 767
Registration VH-OGB
Serial number 24316
Sector Jet
Operation type Air Transport High Capacity
Departure point Hong Kong
Destination Sydney, NSW
Damage Nil

Aircraft details

Manufacturer The Boeing Company
Model 767
Registration ZK-NCF
Sector Jet
Operation type Air Transport High Capacity
Departure point Auckland, NZ
Destination Hong Kong
Damage Nil

Centrum Naukowo-Produkcyjne-PZL M-18, VH-NIJ

Summary

The Australian Transport Safety Bureau did not conduct an on-scene investigation into this occurrence. The report presented below was derived from information supplied to the Bureau and an ATSB laboratory examination of the engine's electrical wiring harness.

On 27 March 2004, while en route to conduct fire bombing operations south-east of Bunbury, Western Australia, the pilot of the Centrum Naukowo-Produkcyjne-PZL Dromader, registered VH-NIJ, noticed the engine begin to falter. With unsuitable terrain ahead, he elected to carry out a forced landing in a small forest clearing. A short time later the engine stopped completely and during the landing the aircraft was destroyed. The pilot exited the aircraft with minor bruising.

The wreckage was recovered to an engineering facility at Jandakot where the engine and its accessories were dismantled and examined. No faults were detected. During examination of the airframe, electrical continuity checks were conducted on the switch leads for the left and right magnetos1. The right magneto switch lead was found to be shorted or grounded to earth (producing the same effect as if the magneto switch was selected to OFF) and the left magneto switch lead was intermittently shorting to earth.

The electrical wiring harness, which exited the engine bay through a steel pipe in the upper right corner of the firewall, was examined and found to have been exposed to localised heating.

The wiring harness was disassembled and both magneto switch leads, which were positioned adjacent to each other in the harness, were found partially fused, due to the melting of their wiring insulation.

The wires were separated out of the harness and forwarded to the ATSB laboratory for closer inspection in an effort to determine the reason for the melted insulation. The examination confirmed that the heating was from an external source. It was not due to electrical power shorting within the wiring harness.

In the absence of any mechanical malfunction identified within the engine or any of its accessories, it is likely that the loss of engine power was the result of grounding of the right magneto switch lead, which switched that magneto off. The engine then faltered as the left magneto switch lead shorted to earth intermittently, depriving the engine of continuous electrical energy to the spark plugs from the remaining magneto.

Further examination of the aircraft could not determine the source of the localised heating of the wiring harness which melted the magneto switch lead insulation. The Civil Aviation Safety Authority advised that a check of the operator's fleet had not revealed similar damage to any other aircraft.

1 A magneto is a component driven by the engine to produce electrical power for the ignition system spark plugs independent of the aircraft electrical system.

Occurrence summary

Investigation number 200401110
Occurrence date 27/03/2004
Location 15 km SE Bunbury, (ALA)
State Western Australia
Report release date 29/09/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Engine failure or malfunction
Occurrence class Accident
Highest injury level Minor

Aircraft details

Manufacturer PZL Warszawa-Okecie
Model M-18
Registration VH-NIJ
Sector Piston
Operation type Aerial Work
Departure point Bunbury, WA
Destination Bunbury, WA
Damage Destroyed

Beech Aircraft Corp 200C, VH-NTH

Summary

On 23 March 2004, shortly after take-off from Katherine, NT, the left main landing gear of the Beech 200 aircraft, registered VH-NTH, did not retract. The flight continued to Darwin with the landing gear extended. During approach to Darwin airport the pilot advised air traffic control that he could not obtain a green `down and locked' indication for the left main landing gear and declared an emergency prior to landing. During touchdown, the left main landing gear collapsed, and the aircraft slewed off the runway. Both occupants evacuated the aircraft with no injuries.

The aircraft operator's maintenance organisation examined the aircraft and found that the left main landing gear drive shaft had severed as a result of fretting against a bleed air duct clamp tail. The bleed air duct clamp (jubilee clamp) had been fitted to the aircraft during an aircraft refurbishment program in September 2003. The jubilee clamp tail had been fastened in close proximity to the landing gear drive shaft. Subsequently, the jubilee clamp tail had come into close contact with the drive shaft, leading to severe wear of the drive shaft section and eventual failure.

As a result of the issues identified with this occurrence, the aircraft operator has conducted a fleet-wide examination of all similar aircraft to ensure adequate clearance exists between bleed air clamps and landing gear drive shafts.

The operator has submitted a major defect report to the Australian Civil Aviation Safety Authority and intends to notify the manufacturer of a number of deficiencies noted in the aircraft maintenance manual.

Occurrence summary

Investigation number 200401024
Occurrence date 23/03/2004
Location Darwin, Aero.
State Northern Territory
Report release date 21/04/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Runway excursion
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Beech Aircraft Corp
Model 200
Registration VH-NTH
Serial number BL-012
Sector Turboprop
Operation type Aerial Work
Departure point Katherine, NT
Destination Darwin, NT
Damage Substantial

Fairchild SA227-DC, VH-HPE, on 22 March 2004

Safety Action

Aircraft maintenance contractor

As a result of this occurrence, the aircraft maintenance contractor has highlighted the occurrence to all engineering staff and required all maintenance engineers to re-familiarise themselves with procedures in relation to critical maintenance tasks, including duplicate inspections.

Aircraft operator

The aircraft operator published an alert to all company pilots reminding them of their responsibility to confirm the correct sense of aircraft flight control systems prior to departure. The operator also instigated a formal mechanism for crews to apply MEL conditions when operating at a remote aerodrome.

Civil Aviation Safety Authority

As a result of this and other similar occurrences, the Australian Civil Aviation Safety Authority advised the US Federal Aviation Administration of the occurrences and published an article titled Nose up, nose down regarding trim switches in the November/December 2004 issue of Flight Safety Australia magazine. The article analyses the cause of these failures and highlights the importance of maintaining switches and following correct procedures to prevent similar occurrences.

Summary

The pilot in command of the Fairchild Industries SA-227 aircraft, registered VH-HPE, operating a scheduled Regular Public Transport flight, reported that excessive forward control column force had been required 'to trim the aircraft nose down' during departure from Sydney Airport.

The Australian Transport Safety Bureau did not conduct an on-scene investigation of this occurrence.

Report

On Monday, 22 March 2004, the pilot in command of the Fairchild Industries SA-227 aircraft, registered VH-HPE, operating a scheduled Regular Public Transport flight, reported that excessive forward control column force had been required 'to trim the aircraft nose down' during departure from Sydney Airport. The pitch trim selector was switched to the copilot position, control was passed to the copilot, who was then able to trim the aircraft, and the flight continued to Taree, NSW.  After landing, an examination by the crew revealed that the pilot in command's (left side) control yoke pitch trim switch was operating in the reverse sense from normal operation.

Discussions were held between the flight crew and the operator's chief pilot and chief engineer and a decision was made to continue with the following two scheduled flights before the aircraft returned to a suitable maintenance facility for rectification.  A subsequent engineering examination revealed that the pilot in command's pitch trim switch had been installed upside-down and had to be removed and re-installed in the correct orientation (refer figure 1).  The pitch trim system was checked for correct operation and the aircraft was returned to service.

Figure 1:  Left side pitch trim control switch

VH-HPE-control-switch.jpg

In the days preceding the occurrence, the aircraft underwent scheduled maintenance at a contractor maintenance facility.  During maintenance, there was a requirement to replace the left side control column pivot bearings.  To access the bearings, it was necessary to remove the control yoke and the control yoke pitch trim switch by de-soldering the switch wiring and removing the switch from the yoke housing.  After the control column bearings were replaced, the control yoke was re-installed and the trim switch wiring was re-soldered to the respective terminals.  The trim switch was then re-installed into the control yoke and the engineers reported that they conducted a full installation and duplicate functional check of the pitch trim system and completed the documentation in the aircraft maintenance worksheets.

During the investigation, the aircraft maintenance engineers responsible for the switch installation and functional check indicated that they had completed the work and that the duplicate functional check was conducted with no apparent discrepancies.  The aircraft was then handed over to other maintenance engineers for the completion of further maintenance tasks.  The following day, the scheduled departure of the aircraft was delayed due to on-going maintenance rectifications.  None of these further maintenance tasks involved the aircraft pitch trim system.  Following the delay, the aircraft departed on the occurrence flight after the crew had conducted pre-flight checks, including a check of the pitch trim system cockpit indication for correct operation.  The aircraft maintenance engineers had been assigned the maintenance tasks away from their normal location on a weekend and the aircraft was required for scheduled operations on the Monday morning.

The maintenance contractor and the aircraft operator conducted separate investigations into the trim switch misalignment and concluded that the only plausible scenario leading to the misalignment was that the engineers responsible for the pitch trim switch installation had installed the switch incorrectly. The discrepancy had not been detected during the installation and duplicate functional checks or the flight crew's pre-flight checks.

The type certificate data sheet holder for the aircraft type reported that the aircraft Minimum Equipment List (MEL) provides no relief for flight with one pitch trim system inoperative and so the decision to continue the scheduled flights in this condition was contrary to the requirements of the operator's flight operations manual.

Occurrence summary

Investigation number 200400998
Occurrence date 22/03/2004
Location Sydney, Aero.
State New South Wales
Report release date 17/05/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight control systems
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Fairchild Industries Inc
Model SA227
Registration VH-HPE
Serial number DC-823B
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Sydney, NSW
Destination Taree, NSW
Damage Nil