Cessna U206A, VH-OWA

Safety Action

The Civil Aviation Safety Authority advised that an article highlighting the importance of placards and emergency procedures had been submitted to the editor of Flight Safety Australia and will be published in a forthcoming edition.

Analysis

It was likely that, in lowering the right wing while passing the airstrip and golf course, the pilot 'slipped' the aircraft in order to counter the aircraft tendency to turn. However, the period of any uncoordinated flight could not be determined. Although the quantity of fuel in the selected tank exceeded the '1/4 tanks or less' quoted in the Owner's Manual caution about uncoordinated flight, there was still a risk of fuel starvation and engine stoppage with 1/3 tank capacity. Given the absence of any evidence of pre-accident aircraft defects or engine mis-handling, it is possible that the engine failure was due to uncovering of the right fuel tank outlets and introduction of air into the fuel system.

While the previous power loss event was of interest to the investigation the lack of specific information about that event meant that a link with the engine failure could not be established.

The pilot's response to the engine failure was based on a generic procedure that was inconsistent with the in-flight engine restarting procedures produced by the aircraft manufacturer. Although the investigation could not determine the status of the auxiliary fuel pump wiring, the information available indicated that the LO function of the fuel pump was capable of producing significant fuel flow. It was likely that sustained use of the auxiliary fuel pump, instead of the momentary use specified by the engine manufacturer, provided fuel flow that exceeded the engine's requirements and prevented a restart. Had the pilot referred to the fuel flow gauge, he could have ascertained the amount of fuel being supplied to the engine, and responded accordingly. The pilot's lack of awareness of the manufacturer's procedures could be attributed in part to the absence of the applicable placard and procedure card in the aircraft and the absence of training in type-specific emergency procedures.

The pilot delayed the search for a specific landing site until the aircraft had descended to about 750 ft, because he was initially focussing on restarting the engine. This was primarily due to the pilot's perception that the engine failure was similar to the previous engine power loss event and his expectation that the engine would eventually restart. Although the pilot managed to reach a clear area, an earlier diversion to a specific landing area after the engine failure would have reduced the risk of a forced landing in a less favourable location.

The tailwind during the glide approach, and the limited amount of flap extension had a positive effect on the aircraft's glide range. However, those two factors contributed to a relatively higher touchdown speed, which increased the risk of aircraft damage and occupant injury. Due to the prevailing wind conditions and the track to the landing area, a tailwind during landing was unavoidable. The spring-loaded flap switch combined with high pilot workload made it difficult for the pilot to further extend flap in the late stage of the approach.

Summary

On 4 June 2004, the pilot of a Cessna Aircraft Company U206A planned to conduct a private flight from Lakeside Airpark to Proserpine aerodrome and return, a total distance of 40 km. The pilot was the only occupant on the flight to Proserpine which he described as uneventful. Three passengers boarded at Proserpine for the return flight via Laguna Whitsunday Resort, a diversion for sightseeing that added a few minutes flight time.

The pilot described the pre-flight engine run-ups and takeoff at Proserpine as normal and said that he was operating on the right fuel tank as he climbed the aircraft to 1,500 ft above mean sea level. About 4 minutes after departure, the aircraft flew parallel to the resort's airstrip construction site, and then passed the golf course and marina. The pilot reported that, for short periods of less than a minute he had banked the right wing 30 degrees down to optimise the view for his passengers, but he could not recall the extent to which opposite rudder1 was applied during those times. Shortly after passing the marina, when the aircraft was flying straight and level and was over water at about 1,200 ft, the engine failed.

The pilot selected the right half (coloured yellow) of the auxiliary fuel pump switch to LO and changed the fuel selector position from the right to left tank. There was no response from the engine so he changed the position of the fuel selector a number of times and selected the left half (coloured red) of the fuel pump switch to HI for short periods.

Figure 1: VH-OWA auxiliary fuel pump switch (centre).

aair200402049_001.jpg

The pilot reported that he didn't refer to the fuel flow gauge, but was convinced that fuel wasn't being supplied to the engine. By this stage the altimeter was indicating 750 ft and he began searching for a specific landing area. The pilot glided the aircraft in a north-westerly direction towards a flat area between the marina and the resort golf course. The wind was from the south-east at about 10 kts. He continued with his attempts to restart the engine and managed to transmit a Mayday late in the approach. Flap was not extended beyond 5 degrees and the pilot reported that he was too busy during the final stage of the approach to hold the spring-loaded flap control switch down.

The stall warning activated just before the aircraft landed heavily on a flat area about 20 m before a 1.4 m high embankment. The propeller dug into the bank and the aircraft overturned, resulting in substantial damage. Witnesses and resort staff attended the scene and helped the pilot and passengers out of the aircraft. Emergency services attended from Proserpine and treated the four occupants, who were seriously injured.

The pilot reported that he was not manipulating any engine controls or switches immediately prior to the engine failure and that there were no prior indications of the failure. An extensive examination of the aircraft including the fuel system, ignition system and engine did not reveal any contaminants or defects that would have contributed to the engine failure. The aircraft's fuel tanks contained approximately 50L of fuel per side, which was about 1/3 of each tank's capacity. Laboratory testing of samples from both tanks identified the fuel as aviation gasoline (AVGAS) and did not identify any characteristics that would have contributed to the engine failure.

The Owner's Manual stated that when selected to LO, the auxiliary fuel pump would only operate when the starter was engaged. However, the pilot advised that when priming the engine prior to starter engagement, the auxiliary fuel pump selected to LO consistently produced at least a 12 gal/hr fuel flow. While this indicated that the aircraft's auxiliary fuel pump wiring did not conform to the manufacturer's specifications, damage to the aircraft prevented an assessment of the pump output and exactly how the fuel pump switch was wired.

A Civil Aviation Safety Authority airworthiness directive (AD), issued by the then Australian Civil Aviation Authority in 1979, mandated action in accordance with a service information letter issued by the aircraft manufacturer. The service letter specified provision of a fuel flow stabilisation placard and associated procedure card in that aircraft model. Although the aircraft logbooks indicated compliance in 1985 with the requirements of the AD, neither the placard, nor the procedure card that included in-flight engine restarting procedures, was in the aircraft. The restart procedures specified that the auxiliary fuel pump be selected to ON or HI until the indicated fuel flow was in the green arc, then it should be selected off. The pilot reported that he was not aware of the requirement for the placard and procedure card, nor was he aware of the type-specific in-flight engine restarting procedures. The copy of the owner's manual that was in the aircraft did not include any emergency procedures.

The pilot related that about 8 months prior to the accident the aircraft had sustained a significant power loss while cruising straight and level at 6,500 ft in calm conditions. He had applied the same engine restart procedure that he used during the accident sequence and after a series of engine power fluctuations eventually accomplished a sustained restart at about 3,000 ft. The pilot believed that there had been a vacuum or blockage and the only way he got the engine to run satisfactorily was to rotate the fuel selector between the left and right tanks using a small amount of boost. There was no reason identified for that power loss and the aircraft operated normally for a further 70 hrs. During that time, a periodic inspection was carried out and no aircraft defects that could have contributed to the power loss were identified.

The owner's manual included the following caution in the description of the fuel system.

... with 1/4 tanks or less, prolonged uncoordinated flight such as slips or skids can uncover the fuel tank outlets, causing fuel starvation and engine stoppage. Therefore, with low fuel reserves, do not allow the airplane to remain in uncoordinated flight for periods in excess of 1 minute.

The ATSB recently completed an investigation into an engine failure resulting from fuel starvation that involved a similar aircraft type (Cessna 207, ATSB report 200403210). That investigation found that the in-flight engine restart procedures published by the manufacturer were not followed, but the engine restarted after a significant height loss of about 700 ft.

1 Application of rudder in the opposite direction to a lowered wing inhibits the development of a turn, resulting in a slip that can allow flight on a straight track. An aircraft that is slipped is considered to be in uncoordinated flight.

Occurrence summary

Investigation number 200402049
Occurrence date 04/06/2004
Location 83 km NW Mackay, (VOR)
State Queensland
Report release date 23/12/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Engine failure or malfunction
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Cessna Aircraft Company
Model 206
Registration VH-OWA
Serial number U2060439
Operation type Private
Departure point Proserpine, QLD
Destination Lakeside Airpark, QLD
Damage Destroyed

Bell Helicopter Co 212, VH-NSA

Summary

The Australian Transport Safety Bureau (ATSB) did not conduct an on-scene investigation of this accident. The accident was investigated by the Civil Aviation Division (CAD) of the Ministry of Transport and Communication Timor Leste (East Timor) which also compiled and released the final report.

On 2 June 2004, at 0725 Coordinated Universal Time, a Bell Helicopter Company 212, registered VH-NSA, was being flown from Dili to the Same village helicopter landing site (HLS), East Timor, to conduct a medical evacuation of a patient from Same to the Dili hospital. The helicopter was being flown by two pilots. Also on board were a helicopter crewman, a doctor and a nurse. The helicopter was reported to have suddenly lost height while manoeuvring in heavy rain during the approach to land at Same. Despite efforts by the pilots to regain airspeed and arrest the descent, the helicopter impacted trees located about 0.5 NM from the Same HLS. The helicopter subsequently impacted the ground and came to rest on its left side. The nurse and the helicopter crewman received serious injuries. The pilot in command, copilot and the doctor received minor injuries.

In accordance with its obligations under Annex 13 to the Convention on International Civil Aviation, the CAD initiated an investigation into the circumstances surrounding the accident.

The CAD requested that the ATSB assist their investigation by providing technical advice and investigation management support. In accordance with Annex 13 paragraph 5.18, the ATSB appointed an Accredited Representative to assist the CAD to obtain details of the pilots' qualifications, operational and technical data and records from Australia. The ATSB also assisted by conducting some interviews by telephone.

The final investigation report titled Aircraft Accident Report Bell 212/UN079/VH-NSA is available from:

Civil Aviation Division of Timor Leste
Ministry of Transport and Communication Timor Leste
Dili East Timor

Occurrence summary

Investigation number 200402038
Occurrence date 02/06/2004
Location 1 km NW Same, Aero. East Timor
State International
Report release date 10/10/2005
Report status Final
Investigation type External Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Miscellaneous - Other
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Bell Helicopter Co
Model 212
Registration VH-NSA
Serial number 30550
Sector Helicopter
Operation type Aerial Work
Departure point Dili, East Timor
Destination Same HLS, East Timor
Damage Destroyed

Boeing 737-376, VH-TJD

Summary

Sequence of events

On 3 June 2004, a Boeing 737-376 (737) registered VH-TJD was tracking on a standard arrival route, descending on the downwind leg for runway 34 at Melbourne Airport. Air traffic control (ATC) had issued the crew with a clearance to descend to 6,000 ft. At the same time, a de Havilland Dash 8 (Dash 8) registered VH-WZI was departing from runway 34, on a standard instrument departure on climb to 5,000 ft. As the 737 levelled at 6,000 ft and the Dash 8 was approaching 5,000 ft, the Dash 8 crew advised ATC that they had received a brief traffic alert and collision avoidance system (TCAS) resolution advisory (RA). The advisory was to climb the aircraft. Before the crew could react, the TCAS indicated that the confliction had been resolved. At the time of the TCAS RA, the aircraft tracks had already crossed and the aircraft were diverging.

The ATSB examined the recorded ATC radar data and the recorded flight data from both aircraft. The data indicated that the minimum lateral and vertical distances between the aircraft were 0.5 NM and 1,300 ft respectively. The required separation standard was either 3 NM or 1,000 ft. There was no infringement of separation standards.

The TCAS manufacturer suggested that the occurrence was indicative of a known problem with TCAS, termed `bump up'. When one aircraft is climbing and approaching a specific level 1,000 ft below another aircraft that is already level, or if an aircraft is descending to and approaching a level 1,000 ft above another aircraft that is already level, `bump up' may trigger a TCAS advisory.

The TCAS tracks intruder aircraft and uses the data calculation to determine the appropriate collision avoidance advisory information. The manufacturer reported that the possibility of an RA depends on the timing of the level-off and the relative distance and vertical rates at that time. The manufacturer also advised that the latest upgrade to the TCAS logic had reduced, but not eliminated, `bump-up' occurrences.

Examination by the ATSB and the manufacturer of the actual separation between the aircraft did not reveal any reason a TCAS RA should have been issued. The reason the Dash 8 crew momentarily received a climb advisory when they were climbing towards the level of the 737 and diverging from it could not be determined.

Occurrence summary

Investigation number 200402025
Occurrence date 03/06/2004
Location 6 km W Melbourne, (VOR)
State Victoria
Report release date 09/11/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category ACAS warning
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 737
Registration VH-TJD
Serial number 24298
Sector Jet
Operation type Air Transport High Capacity
Departure point Brisbane, QLD
Destination Melbourne, VIC
Damage Nil

Aircraft details

Manufacturer De Havilland Canada/De Havilland Aircraft of Canada
Model DHC-8
Registration VH-WZI
Serial number 014
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Melbourne, VIC
Destination Devonport, TAS
Damage Nil

Powerplant/propulsion event, 40 km south of Tobermorey, Northern Territory, on 30 May 2004, Robinson R22 Mariner II, VH-MIB

Safety Action

4 Safety Action

4.1.1 Robinson Helicopter Company

In July 2006, the Robinson Helicopter Company issued Safety Notice SN-40, titled "Post crash Fires".  That Safety Notice states:

There have been a number of cases where helicopter or light plane occupants have survived an accident only to be severely burned by fire following the accident.  To reduce the risk of injury in a post-crash fire, it is strongly recommended that a fire-retardant Nomex flight suit, gloves, and hood or helmet be worn by all occupants.

Conclusions

3 Conclusions

3.1 Findings

  • There was no witness or mechanical evidence to indicate any problems with the flight controls, fuel system or engine prior to the event.
  • Failure of the forward flex plate resulted in drive to the main rotor gearbox being partially disconnected.
  • The failed forward flex plate coupling punctured one or both the helicopter fuel tanks and the stainless steal engine compartment firewall.
  • The helicopter settled heavily and impacted with terrain.
  • The helicopter was destroyed by impact forces and a post-impact fire.
  • Egress from the helicopter was hampered by the unusual attitude of the cabin which caused extended exposure of the survivor to the post-impact fire.

3.2 Significant factors

One of the two bolted joints linking the flex plate to the main rotor gearbox yoke in the forward flexible coupling was previously assembled incorrectly, resulting in a lack of clamping force and subsequent fatigue failure of the flex plate and loss of drive to the main rotor gearbox.

Analysis

2 ANALYSIS

2.1 Helicopter

The initiating event in the occurrence sequence was the failure of the flex plate in the forward flexible coupling. That event was the source of the loud noise that the passenger reported hearing. Once the plate failed, the clutch shaft yoke was retained at one end only.  As a result, the diameter of the yoke and flex plate effectively doubled, allowing those rotating components to contact and puncture the fuel tanks and the horizontal stainless steel fire wall, as observed in the wreckage examination. Fuel leaking from the punctured tanks and firewall, would have fed directly into the engine compartment. The evidence indicates that the fuel then contacted either a hot engine component or some other source of ignition, which could have resulted in the helicopter being on fire before impact. The soot pattern on the ground confirmed that fuel from the punctured tanks was being ejected from the helicopter at first impact with the ground. The fuel may have ignited while the helicopter was still airborne or flash back could have occurred after impact.

One of the bolted joints in the forward flexible coupling had been assembled incorrectly, resulting in a lack of clamping force and subsequent fatigue failure of the flex plate in the forward flexible coupling and loss of drive to the main rotor gearbox.

The build records and digital photographs supplied by the manufacturer showed that the assembly of this joint at the factory had been correct.

Examination of the maintenance history of the helicopter revealed that, while maintenance had been performed on the drive system on a number of occasions since factory assembly, there was no recorded documentary evidence found that any subsequent maintenance had been performed on the particular bolted joint where the failure occurred. The stated procedure employed by the engineer who carried out AD/R22/51 was appropriate and consistent with accepted practices and did not require disassembly of the bolted joint that failed.

Examination confirmed that both tail rotor blades failed as a result of contact with the ground during the impact sequence.

At the time of the incident the helicopter was being operated close to the ground with low forward air speed. That would have left the pilot with little time to respond effectively to failure of a critical flight system such as the main rotor drive system.

The manner in which the failure of the forward flex plate occurred resulted in an unusual emergency situation for the pilot. As well as the obvious noise and out of balance caused by the still rotating but partially separated forward flexible coupling, symptoms would have included a failure of the drive to the main rotor gearbox resulting in decreasing main rotor speed and a nose-left yaw. That was consistent with some of the symptoms normally associated with an engine failure. However, in this case the engine had not failed and initially would have presented the pilot with additional and potentially confusing symptoms. Those symptoms would have included an initial indication of engine overspeed, and continuing tail rotor drive.

The normal response to an engine failure, and also relevant in this case, would be for the pilot to lower the collective control in order to recover any loss of main rotor RPM. The pilot would then allow the helicopter to enter an autorotation descent. If there was insufficient height for the descent to stabilise, main rotor RPM would not have recovered before the pilot commenced the touchdown phase of the autorotation. Low main rotor RPM during the touchdown phase would have decreased the possibility for the pilot to reduce the helicopter's rate of descent and carry out a safe touchdown. It is evident that fatigue cracking in the flexplate initiated at the bolthole and propagated under the washers of the bolted joint towards the edge of flexplate. It was also evident from the fracture surface features that crack growth had occurred over a number of flights prior to the accident flight. Because cracking occurred under the washers in the bolted joint, the opportunity to detect cracking by a pre-flight visual inspection would have been limited to the detection of a crack at the edge of the flexplate arm.

The reliability of a general visual inspection (for example, a pre-flight inspection) is affected by lighting, the ability to get close to the component (proximity), and dirt and dust from the operating environment. Reliable detection of a specific defect would require a directed detailed inspection.

2.2 Survival

The crush damage observed to the right side of the cabin structure showed that impact forces were greater on the right side of the helicopter than the left. As a result, the pilot, who occupied the right seat, was subjected to higher impact forces than the passenger in the left seat. The impact forces in this accident were not directly aligned with the helicopters fore-aft and vertical axes. Hence, the level of protection afforded by the seat/harness combination was reduced and probably contributed to the injuries sustained by the pilot. The extent of the post-impact fire precluded any definite conclusions as to what, if any, material may have been carried under the pilot's seat.

When the helicopter came to rest on its right side, the seat in which the passenger was trapped was in an elevated position and was severely affected by the fire. It was also likely that the difficulty the passenger experienced in escaping from the helicopter was due, at least in part, to him being suspended by the safety harness. The time it took the passenger to release himself contributed to the extent of his burn injuries.

The passenger, although seriously injured himself, walked approximately 8 km to summon help. Unfortunately, due to the accident site's remote location, the pilot succumbed to his injuries before medical assistance could reach him.

2.3 Communication equipment

No record of fitment of a fixed Emergency Locator Transmitter (ELT) could be found in the logbooks for the accident helicopter and no ELT unit remnants for either a fixed or personal unit were identified within the main wreckage. Given the intensity of the post-impact fire, it was probable that, had a fixed ELT been fitted, it would have only operated for a very short period of time before being destroyed.

If the pilot was carrying a personal ELT at the time, it is possible that it separated from his person either during the impact or during egress from the wreckage and was destroyed in the subsequent fire.  In addition, if the occupants carried a satellite telephone, it may have reduced the time taken to summon assistance.

Factual Information

1 FACTUAL INFORMATION

1.1 Sequence of events1

At about 1100 Central Standard Time on 30 May 2004, a Robinson R22 Mariner II helicopter, registered VH-MIB, crashed and caught fire while being operated on a fence inspection flight at Tobermorey Station, NT. The pilot sustained fatal injuries, and the passenger was seriously injured.
The passenger reported that the purpose of the flight was to inspect a fence line bordering the property and then to conduct cattle mustering operations. The helicopter was refuelled to full tanks prior to departure. The weather was fine and sunny, with a slight breeze from the south-east.
The passenger reported that while overflying a section of the fence line about 45 km south of the homestead at 30 to 40 ft above ground level, the pilot initiated a turn back to the left to enable a closer look at a particular section of fence. Part way through the turn there was a loud bang from behind the cabin, followed by "horrendous vibration" and the helicopter immediately began to yaw left and descend. The ground marks showed that the tail rotor blades contacted the ground first and then the forward section of the helicopter's right skid struck the ground, disrupting the front section of the cabin. The helicopter then came to rest on its right side and fire rapidly spread to engulf the cabin area.

The pilot was able to free himself from the helicopter through the broken front section of the cabin, but the passenger experienced difficulty undoing his safety harness and remained trapped. He was eventually able to free himself and joined the pilot at some distance from the wreckage. The passenger reported that he assessed the pilot to be badly injured and directed him to a nearby water hole. The passenger then walked to a water bore approximately 8 km from the accident site, where he met other station personnel. The pilot was deceased when medical assistance arrived at the accident site some hours later.

The passenger reported that he had flown in the helicopter several times. During the last few flights before the accident, and during the accident flight itself, he had detected a vibration that he considered abnormal. The passenger advised the investigation that he had conveyed these concerns to the pilot, who advised that he conducted a good check of the helicopter and was satisfied that there were no problems.

1.2 Wreckage examination

Examination of the wreckage by the Australian Transport Safety Bureau (ATSB) investigation team at the accident site (Figure 1) confirmed that the helicopter was yawing left and moving forward when it struck the ground. The tail rotor blades contacted the ground first. The helicopter then contacted the ground slightly nose down and heavily onto the right skid, causing it to separate from the helicopter. The ground impact marks showed that the helicopter continued to yaw left though about 180 degrees after it struck the ground, before coming to rest on its right side. The majority of the cabin and engine bay, including the entire floor area and cabin structure beneath the pilot and passenger seat positions were destroyed by fire.

Figure 1: Helicopter wreckage (arrow indicates bulkhead deformation behind pilot seat position)

aair200401917_001.jpg

The extent of fire damage meant that a complete examination of the helicopter was not possible. Some aluminium components such as tubing in the flight control system had been destroyed. However, all steel components in the control systems for the main and tail rotor were identified and damage to all of these components was consistent with impact forces or fire. The main rotor blades exhibited damage consistent with low rotor energy at impact. Both tail rotor blades had fractured approximately 1/4 span outboard of the rotor hub centre drive (Figure 2). The failed section of one blade was found adjacent to the main wreckage. The failed section of the other blade was found subsequently about 70 m from the main wreckage. Both blade sections were taken to the ATSB laboratories for further examination.

Figure 2: Tail rotor damage

aair200401917_002.jpg

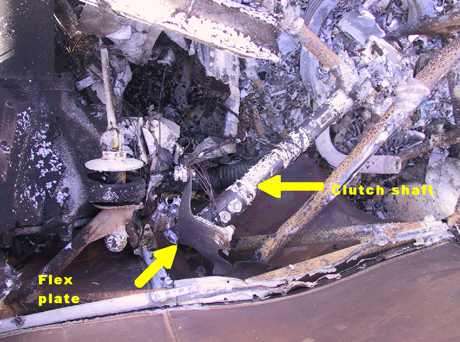
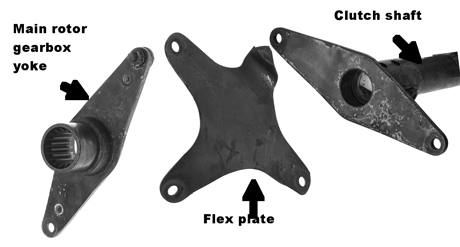
All of the engine drive system components were identified within the wreckage. The flex plate for the forward flexible coupling of the main rotor drive system was fractured at one of the two attachment points to the main rotor gearbox yoke (Figure 3 and 4). The flex plate, including the clutch shaft, were retrieved from the accident site, for further examination. The flex plate for the intermediate flexible coupling was intact and showed evidence of rotational damage consistent with partial drive system power at impact. The rear flex plate and coupling components were also found intact.

Figure 3: Forward flexible coupling as found in wreckage

aair200401917_003.jpg

Figure 4: Components of failed forward flexible coupling

aair200401917_004.jpg

The fuel system and engine ancillaries were destroyed by the fire. There were vertical cuts puncturing the inside wall of the right fuel tank and the horizontal stainless-steel firewall above the engine. The cuts in the right tank and the firewall aligned with the forward flex plate plane of rotation (Figure 5). The left fuel tank was destroyed by fire.

Figure 5:  Flex plate puncture of stainless-steel firewall above engine.

aair200401917_005.jpg

1.3 Personnel information

The pilot held a commercial pilot (helicopter) licence and was appropriately endorsed on the R22. He was issued with a private pilot (aeroplane) licence in 1974 and a commercial pilot (helicopter) licence in 1990. The pilot was issued with a commercial pilot (aeroplane) licence in 1995. He held a stock mustering rating and a valid class 1 medical certificate. He completed a flight review in the occurrence helicopter on 19 April 2004. At the time of the accident, the pilot had approximately 10,400 hours aeronautical experience. He flew 31 hours in the occurrence helicopter between 17 and 30 May 2004.

1.4 Medical and pathological information

Postmortem and pathology reports did not indicate that the pilot was suffering from any condition that might have affected his performance during the flight. The most significant injuries sustained by the pilot were the result of impact forces rather than fire.

1.5 Fire

There was a fire affected area (sooting) on the ground that extended up-slope from the wreckage (Figure 6). The sooting formed a swirl pattern of decreasing radius in the direction the helicopter was yawing when it contacted the ground.

Figure 6:  Sooting pattern adjacent to wreckage (arrow indicates approximate direction of flight at impact)

aair200401917_006.jpg

1.6 Survival aspects

Three-point lap/sash type safety harnesses were fitted to both seating positions in the helicopter. The passenger reported that both he and the pilot had their harnesses fastened during the flight. Fire damage precluded a detailed assessment of the seats and performance of the crush zones beneath them as well as the seat belt harnesses.

Severe crush damage to the lower cabin bulkhead was evident immediately behind the pilot's seat. (Figure 1).

Following the accident, no Emergency Locator Transmitter signal was received (refer section 1.7.6). There was no mobile telephone coverage in the area and the passenger reported that they did not carry any other communications aids, such as a portable satellite telephone.

1.7 Helicopter information

1.7.1 Helicopter data

The helicopter was manufactured in August 2002 as Serial No 3357M. The most recent maintenance release for the helicopter could not be located. It was reported to have been kept in the helicopter. If so, the maintenance release would have been destroyed in the post-impact fire. Based on other maintenance records and information contained in the pilot's personal diary, the total time in service of the helicopter on 30 May 2004 was estimated to have been 506 hours.

1.7.1 Main and tail rotor drive system

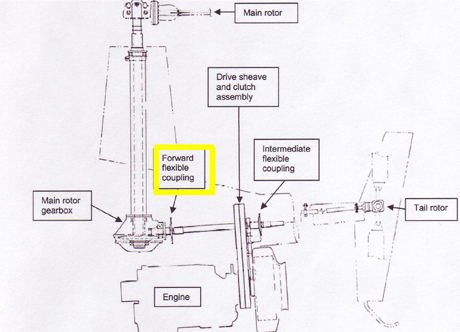
In the R22 helicopter, power to drive the main and tail rotors was transmitted from the engine to the rotor drive train via a multiple Vee belt drive and clutch system. A shaft transmitted power forward from the clutch to the main rotor gearbox and aft to the tail rotor gearbox (Figure 7).

Figure 7:  Main components of main and tail rotor drive systems2

aair200401917_007.jpg

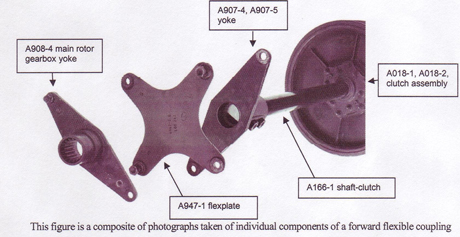
A forward flexible coupling, which includes a flex plate, connected the drive shaft to the main rotor gearbox.  The tail rotor drive system also included an intermediate and a rear flexible coupling. Yoke assemblies at the end of each drive shaft section connected the shaft to the flex plate via bolted joints (Figure 8). The purpose of these flex plates was to accommodate small differences in shaft axial alignment during drive shaft rotation. The flex plates and the bolted joints were critical elements in drive system integrity.

Figure 8:  Components of the forward flexible coupling

aair200401917_008.jpg

The helicopter manufacturer published procedures for assembling and aligning the drive system components, including the allowed tolerances. The design loads of components could be exceeded if those tolerances were not met.

1.7.3 Helicopter manufacture

The helicopter arrived in Australia partly disassembled for ease of shipment. The main drive system components within the engine compartment were assembled during manufacture and not subsequently disturbed for this method of international shipment.

In order to assist the investigation, the manufacturer supplied the investigation with the itemised build records, which included digital photographs of the rotor drive system, for the occurrence helicopter. Those records were reviewed as part of the laboratory analysis of the flexible coupling failure. The review of the build records and photographs for the forward flexible coupling in the occurrence helicopter showed that NAS6605-6 bolts had been used, and a spacer washer had been included in each bolted joint and one thin washer had been installed under the nut, with a palnut (locking nut) fitted to each. The build records showed that the build-up of the bolted joint at the time of manufacture of the helicopter was correct and in accordance with the assembly procedures.

The 'Daily or Preflight Checks' section 4-2 and 4-3 of the manufacturers Pilot's Operating Handbook identified the requirement for a visual check of the flex coupling to ensure there are 'No cracks and 'Nuts tight'. Also required is a check of the yoke flanges for cracking. It further advised, in part, that 'During the following inspection, check the general condition of the aircraft and also look for any evidence of leakage, discolouration due to heat, dents, chafing, galling, nicks, corrosion and especially for cracks. Also check for fretting at seams where parts are joined together. Fretting of aluminium parts produce a fine black powder, while steel produces a reddish brown or black residue'.

1.7.4 Maintenance history

Maintenance records indicated that an Australian certificate of airworthiness for the helicopter was issued on 11 October 2002, after assembly in Australia, following manufacture and acceptance flights in the US.  At that time, the total time in service was 5.1 hours. A summary of subsequent maintenance conducted on the helicopter is as follows. All references to drive system adjustments and/or maintenance have been included.

  • 11 March 2003. Total time in service 55.1 hours.  50 hourly engine inspection
  • 27 March 2003. Total time in service 98.5 hours.  100 hourly inspection.  Maintenance carried out included adjustment of the engine sheave alignment.3
  • 30 June 2003. Total time in service 198.2 hours.  100 hourly inspection.  Maintenance carried out included checking and adjustment of the engine sheave alignment and intermediate flex plate shimming to within limits.
  • 15 September 2003.  Total time in service 296 hours.  100 hourly inspection.
  • 17 February 2004. Total time in service 384.1 hours.  Civil Aviation Safety Authority Airworthiness Directive (AD) R22/51 'Main Rotor Clutch Shaft', dated 12 November 2003, was incorporated. AD/R22/51 was applicable to all R22 helicopters. It required disassembly of the main rotor yoke (A907) to the clutch shaft joint (A166) (see Figure 6) and inspection of the shaft and yoke for damage including fretting4 of bolt holes, cracking in the area of the bolt holes, and the presence of an unapproved jointing compound in the mating surfaces. The helicopter maintenance worksheet indicated that no fretting was evident but that the incorrect jointing compound had been used. The worksheet stated that the AD had been complied with and that the clutch shaft and yoke were reassembled in accordance with the maintenance manual. The worksheet also recorded that a duplicate inspection of the clutch shaft installation and the yoke (A907) assembly had been performed. The licensed aircraft maintenance engineer who carried out the AD reported that he disconnected the yoke (A907) from the forward flex plate, but did not disconnect the flex plate from the main rotor gear box yoke (A908). He stated that he did not perform any maintenance on the bolted joints at the connection between the main rotor gear box yoke and the flexible coupling.
  • 27 March 2004. Total time in service 396 hours.  100 hourly inspections.  Maintenance carried out included engine sheave alignment.
  • 12 May 2004. Total time in service 476.1 hours.  100 hourly inspections.

The documentation showed that maintenance had been performed on 27 March 2003, 30 June 2003, and 17 February 2004 in the vicinity of the forward flexible coupling that, while it did not specifically necessitate bolt removal, provide opportunities for the forward flexible coupling bolts to be disturbed.

1.7.5 Forward flex plate bolted joint component specification

A review of the diagrams contained in the manufacturer's Maintenance Manual and the Illustrated Parts Catalogue (IPC) revealed a difference in the specifications of the parts in the bolted joints. Notes contained within the IPC explained that bolts of different grip lengths and washers of different thickness were to be used in the flex plate bolted joints to expose between two and four threads beyond the end of the nut. A table comparing the different specifications between the Maintenance Manual table and the IPC is provided in section 4.1.3 of the ATSB technical analysis report attached as Appendix 1.

The manufacturer advised that the bolt length identified in the Maintenance Manual was for use in an earlier version of the manual and was out of date. Corrective action to update this information was scheduled by the company for November 2005, but at the time of writing of this report had not been accomplished.

The manufacturer advised that the company did not publish any warning to maintenance organizations about the discrepancy in bolt length between the Maintenance Manual and the Illustrated Parts Catalogue.  The discrepancy was not considered by the manufacturer to be critical in that the use of either a NAS6605-5 or a NAS6605-6 bolt with the appropriate combination of spacer and washers would give the correct clamp up for proper joint integrity. In the few cases where the -5 bolt did not allow proper installation of the B330-16 palnut, the problem would be self-evident. The manufacturer believed that any engineer performing the installation where the bolt was too short to install a palnut would install a longer bolt or make inquiries to resolve the problem.

1.7.6 Emergency locator transmitter

The maintenance records indicate that the helicopter was imported from the US and subsequently operated by various owners without a fixed Emergency Locator Transmitter (ELT) unit being fitted. This fact was noted on the maintenance releases issued at 5.1 airframe hours total time in service (TTIS) on 11 October 2002 and 98.5 hours TTIS on 27 May 2003, which required the pilot to observe the requirements of CAR 252 and carry a personal ELT. No further entries of this nature were found on maintenance releases issued after this date, nor could evidence be found in the aircraft logbooks that an ELT had been fitted. A search for both a fixed and personal ELT within the wreckage and surrounding accident site was conducted but nothing was found.
The passenger stated that the pilot normally carried a personal ELT on him. No personal ELT was identified among the pilots clothing or personal effects and no emergency signal was received by AusSAR from that location on the day.

1.8 Specialist examination of the failed components

The forward flex plate and the broken sections of the tail rotor blades were subject to detailed examination by the ATSB. The report on those examinations and analysis of the failures is attached as Appendix 1.

The metallurgical evidence confirmed that the failure mode of both tail rotor blades was very similar and was the result of contact with the ground during the impact sequence. The rocky material embedded in the blade tips provided clear evidence that the blades had struck the ground while rotating. The blade that was found about 70 m from the wreckage was thrown that distance as the result of tail rotor rotational energy.

The specialist examination found that the flex plate in the forward flexible coupling fractured as a result of the propagation of a fatigue crack at one of the bolted connections between the plate and main rotor gearbox yoke. Final fracture of the flex plate occurred during operation and not as a result of the collision with the ground. No crack growth or wear damage was observed at the three remaining boltholes. Examination of the bolt installed at the failure location revealed that extensive fretting wear had occurred around the entire circumference of the bolt, in the region adjacent to the flex plate and the regions adjacent to the reinforcing plates. Fretting wear was also evident on the washer surface adjacent to the bolt head.

The bolted joint at the flex plate failure location was found to have a single thin washer under the bolt head and nut, and no spacer washer between the yoke and flex plate. This spacer and washer combination was different from that specified by the manufacturer for use with a NAS6605-6 bolt.

  1. Only those investigation areas identified by the headings and subheadings were considered to be relevant to the circumstances of the accident.
  2. Diagram with permission of Robinson Helicopter Company.
  3. Drive Vee belts sometimes stretch when new and adjustments are then necessary to maintain the correct drive system alignment. Engine sheave alignment is part of that adjustment process.
  4. The AD defined major fretting as 'any evidence of the machining marks in any of the bolt holes being partly or fully obliterated'.

Summary

The crew of the Robinson R22 helicopter were undertaking a fence line inspection at about 30 to 40 ft above ground level. The crew had initiated a turn back along the fence line for a closer look at a particular section of fence. During the turn, a loud bang was heard, and the helicopter began to rotate quickly before striking the ground.

Both occupants were able to exit the helicopter unaided after it came to rest but sustained serious injuries and burns as a result of a post-impact fire. The pilot subsequently died of his injuries.

The investigation found that one of the bolted joints linking the forward flexible coupling flex plate to the main rotor gearbox drive shaft yoke had been assembled incorrectly. This resulted in subsequent fatigue failure of the flex plate and loss of drive to the main gearbox. Control of the helicopter was then lost at a height from which it was difficult to recover.

The crew of the Robinson R22 helicopter were undertaking a fence line inspection at about 30 to 40 ft above ground level. The crew had initiated a turn back to the left, along the fence line for a closer look at a particular section of fence. During the turn, a loud bang was heard, and the helicopter began to yaw quickly before striking the ground.

Both occupants were able to exit the helicopter unaided after it came to rest but sustained serious injuries and burns as a result of a post-impact fire. The pilot subsequently died of his injuries.

Examination of the helicopter wreckage revealed that both tail rotor blades had failed due to contact with the ground.  In addition, the flex plate in the forward flexible coupling of the main rotor drive was found fractured at one of the two attachment points to the main rotor gearbox yoke. The tail rotor blades and several components from the main rotor drive were recovered for detailed analysis in order to resolve the mechanism of fracture and the sequence of failure.

The flex plate in the forward flexible coupling fractured due to the propagation of a fatigue crack at one of the bolted connections between the plate and main rotor gearbox yoke. Final fracture of the flex plate occurred during operation and not because of the collision with the ground. There was no crack growth or wear damage evidence at the three remaining boltholes. Examination of the bolt installed at the failure location revealed that extensive fretting wear had occurred around the entire circumference of the bolt, in the region adjacent to the flex plate and the regions adjacent to the reinforcing washers. Fretting wear was also evident on the washer surface adjacent to the bolt head. This type and degree of wear damage was indicative of operation with insufficient clamping force in the bolted joint.

A review of the manufacturer's original build-sheets for the forward flexible coupling in the occurrence helicopter revealed that NAS 6605-6 bolts were used, and a spacer washer had been included in each bolted joint and one thin washer had been installed under each nut with a palnut (locking nut) fitted to each.

Examination of the forward flexible coupling retrieved from the accident site, found that the bolted joint had been assembled with a washer and spacer combination that was different from that identified by the manufacturer's original build records. These differences indicated that it was likely that the joint had been disassembled and reassembled during a maintenance action subsequent to assembly in the manufacturer's facility.

Occurrence summary

Investigation number 200401917
Occurrence date 30/05/2004
Location 40 km S Tobermorey, (ALA)
State Northern Territory
Report release date 24/08/2006
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22
Registration VH-MIB
Serial number 3357M
Sector Helicopter
Operation type Aerial Work
Departure point Tobermorey Station, NT
Destination Tobermorey Station, NT
Damage Substantial

Flight below minimum altitude, Boeing 737, VH-VBX, 41 km south-south-east of Cairns, Queensland, on 27 May 2004

Safety Action

As a result of this occurrence the operator issued a Flight Crew Operational Notice in response to the occurrence warning crews that:

…it is essential that the approach is correctly entered into the FMC and the appropriate vertical path is checked on the LEGS page.

The operator has advised that it is taking action to amend the Operations Manual to expand the requirements for the PNF to provide support calls of altitude and distance from the IAF.

Significant Factors

  1. The crew did not detect the FMC data entry errors.
  2. The crew did not apply effective crosschecking procedures following FMC modification.
  3. The PNF was not required to provide any altitude or distance support calls during the approach until after the FAF.

Analysis

When the crew of the 737 inadvertently omitted waypoint/altitude constraint data from the flight management computer (FMC) LEGS page, they received no warning from the FMC. The only way to safeguard against this type of erroneous data manipulation is the application of standard operating procedures (SOPs) for FMC data entry and cross-checking.

Additional defences could be achieved by implementing SOPs for the monitoring of flight profile throughout critical stages of flight. The operator had published instructions requiring crew members to provide support calls from the Final Approach Fix (FAF). As a consequence, no calls were initiated by the pilot not flying (PNF) until well after the aircraft had descended below 6,500 ft.

The benefits of adhering to a proven set of SOPs are well documented. The procedures must be appropriate, well understood, and complied with.

Factual Information

The crew reported that when they made preparations for descent the Cairns Automatic Terminal Information Service (ATIS) nominated runway 15 for landing. The crew selected the appropriate approach and landing charts and programmed the flight management computer (FMC) for an arrival to runway 15.

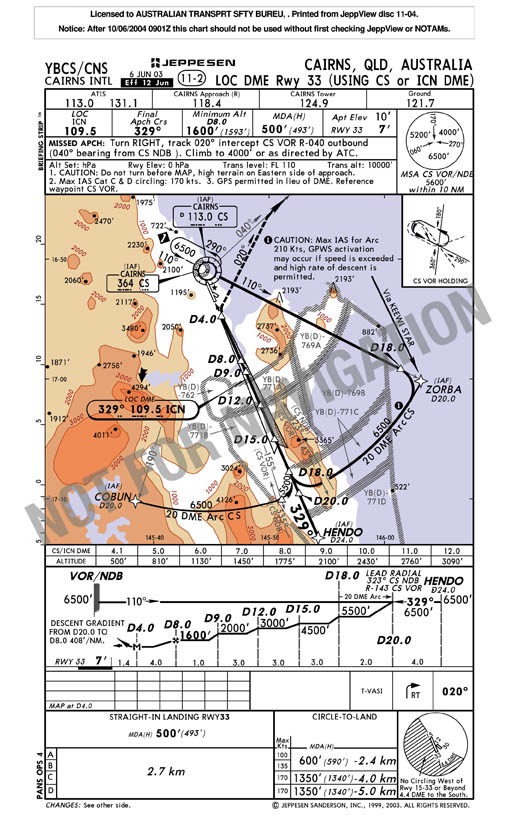
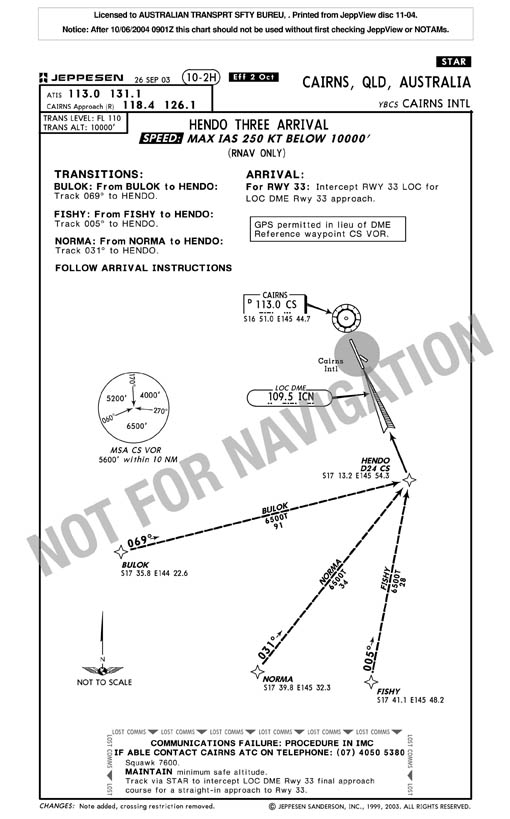
Three minutes before the crew commenced descent, the ATIS was changed to indicate that arriving aircraft from the south could expect to carry out the runway 33 Locator/Distance Measuring Equipment (LOC/DME) approach to runway 33. The crew was not aware of the change to the landing runway until the air traffic controller assigned the crew a HENDO-Three standard instrument arrival (STAR) which included a NORMA transition. In order to comply with the STAR, the 737 was required to proceed via waypoint NORMA and then track 031 degrees to waypoint1 HENDO, which, as the last waypoint of the STAR, also became the initial approach fix (IAF) for the runway 33 LOC/DME approach (Refer figure 1 & 2).

The crew selected the STAR and the runway 33 LOC/DME approach from the FMC navigation database and incorporated the required tracking and altitude requirements into the active FMC-LEGS page. During that interaction the crew did not select waypoint HENDO as the IAF when prompted by the FMC to do so and consequently critical 'Not below 6,500 ft' altitude constraints at the HENDO and 20 DME Cairns waypoints were omitted. The STAR and runway 33 LOC/DME approach became part of the FMC active flight plan and the FMC provided the crew with lateral and vertical navigation guidance.

While on descent, the crew was instructed by air traffic controller to reduce speed and fly a heading that would take the aircraft away from the published STAR track. The crew subsequently reported that this was done to ensure separation with preceding traffic. Once the required separation had been achieved, the crew was instructed to rejoin the localiser approach. They modified the route legs (RTE LEGS) page of the FMC by selecting track direct (TRK DCT) to HENDO. That action removed waypoints from the active route that were no longer required.

At 24 DME, the FMC calculated descent point, the aircraft left 6,500 ft. That occurred because the waypoints and their associated altitude constraints, which ensured that the aircraft would not descend below 6,500 ft until passing 20 DME had been omitted. The autopilot was engaged with vertical navigation (VNAV) mode active.

Analysis of information recovered from the flight data recorder showed that the 737 passed 20 DME Cairns at an altitude of 5,860 ft. The crew reported to air traffic control (ATC) that they were in cloud.

Figure 1: Cairns LOC DME Rwy 33

aair200401904_001.jpg

Reprinted with permission of Jeppesen Sanderson Inc.

Figure 2: Cairns - HENDO THREE ARRIVAL

aair200401904_002.jpg

Reprinted with permission of Jeppesen Sanderson Inc.

Cairns runway 33 LOC/DME approach

To ensure appropriate terrain clearance, flight crews conducting the Cairns runway 33 LOC/DME approach must maintain track within appropriate tolerances and not descend below the minimum altitude specified on the instrument approach chart until passing the next step-down point. Once the next step-down point has been passed, the aircraft is permitted to descend to the next lower minimum altitude. That allows crews to progressively descend, remaining safely clear of terrain as the aircraft approaches the airport for landing.

In order to accommodate aircraft arrivals from various directions, the Cairns runway 33 LOC/DME approach has a number of IAFs. Depending on the STAR issued by ATC, the crew should operate the aircraft to track via COBUN, HENDO, or ZORBA. The IAF forms an integral part of the runway 33 LOC/DME approach.

Flight Management Computer

The FMC system fitted to the 737 provided lateral and vertical flight path guidance as well as performance information to the crew. The FMC can also provide control and guidance information to the autopilot.

The 737 autopilot and flight director system has a number of descent modes. The crew reported that they conducted the Cairns runway 33 LOC/DME approach using VNAV2 path.

Before the crew could utilise the FMC to provide vertical navigation guidance, the FMC needed to compute a descent path, which conformed to the requirements of the instrument approach. Waypoints and associated altitude constraints required by the FMC to compute an accurate approach profile that corresponded to the LOC/DME approach path gradient had been inadvertently omitted by the crew.

The FMC database contained the Cairns runway 33 LOC/DME approach, which the crew selected. They were then prompted to select from one of three transitions; COBUN, HENDO, or ZORBA. During the occurrence flight, the FMC operated as designed.

Communication of safety information

The Operator's Operations Manual included detailed instructions to ensure that crews selected the HENDO transition when activating the runway 33 LOC/DME approach into the FMS.

The operator experienced similar events on three occasions during December 2003. In response to those occurrences the operator produced an article for its Safety Shorts Operational newsletter, which warned crews to follow published procedures when conducting a Cairns runway 33 LOC/DME approach.

The operator's manuals contained the following instruction:

The 737 Flight Crew Training Manual (FCTM)
Set all mandatory altitude restrictions and at or above constraints in the MCP altitude window. The next altitude may be set when the restriction has been assured, and further clearance has been received.

The Flight Crew Operations Manual (FCOM) (Part B) Volume B1 Approaching intercept heading, select flaps 5 and select LNAV or other appropriate roll mode. Approaching the FAF, select gear down and flap 15. Set the [altitude] minima in the MCP altitude window.

Crew communication during instrument approaches

The FCOM issued to crew members referred to the crewmembers as either the pilot flying (PF) or pilot not flying (PNF) and contained the following instruction regarding support calls:

Operations Manual (Part B) 2.11.3.9
On a non-ILS instrument approach, including DME Arrival, the PF shall brief the descent profile to be flown from the Final Approach Fix (FAF). After passing the FAF, the PNF shall call the profile (distance/altitude) at each published or briefed distance/altitude. The PF shall acknowledge the call and initiate any profile correction. The PNF shall then call the next profile distance/altitude.

Note: In the case of the Cairns 33 LOC/DME approach the FAF is at 8 DME.

The PNF was required to provide support calls (of distance/altitude) from the FAF. No calls were required to be made between the IAF, and the FAF. In the case of the Cairns runway 33 LOC/DME approach, the aircraft may be as low as 1,600 ft (the minimum altitude at 8 DME) before any calls were required to be made. The aircraft was between the IAF and the FAF when it descended below 6,500 ft.

  1. Predetermined and accurately known geographical position forming start or end of route segment.
  2. Vertical navigation mode

Summary

On 27 May 2004, a Boeing 737-705 (737) aircraft, registered VH-VBX, was being operated on a scheduled passenger service from Melbourne, Vic, to Cairns, Qld, in instrument meteorological conditions.

Occurrence summary

Investigation number 200401904
Occurrence date 27/05/2004
Location 41km SSE Cairns, Aerodrome
State Queensland
Report release date 25/10/2005
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight below minimum altitude
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 737
Registration VH-VBX
Serial number 29092
Sector Jet
Operation type Air Transport High Capacity
Departure point Melbourne Victoria
Destination Cairns Queensland
Damage Nil

Robinson R22 Alpha, VH-JWG

Summary

The Australian Transport Safety Bureau did not conduct an on scene investigation of this occurrence. The information presented below was obtained from information supplied to the Bureau.

The pilot of the Robinson Helicopter Co R22 Alpha reported that on 23 May 2004 while operating at Scott Creek Station, he hot re-fuelled the helicopter from a bulk fuel tank installation in preparation for mustering. During the into-wind transition from the hover to forward flight, the helicopter rolled rapidly to the right and impacted the ground. The pilot sustained minor injuries and the helicopter was destroyed. He reported that the fuel hose had disconnected from the bulk fuel outlet. It was likely that the helicopter had become entangled with the re-fuelling hose and pump during the departure.

Occurrence summary

Investigation number 200401866
Occurrence date 23/05/2004
Location Scott Creek Station
State Northern Territory
Report release date 30/06/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Minor

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22 Alpha
Registration VH-JWG
Serial number 0414
Sector Helicopter
Operation type Aerial Work
Departure point Scott Creek Station, NT
Destination Unknown
Damage Destroyed

Boeing 737-376, VH-TAH

Summary

The Australian Transport Safety Bureau did not conduct an on scene investigation of this occurrence. The information presented below was obtained from information supplied to the Bureau.

The crew of a Boeing 737, registered VH-TAH, reported that, on 15 May 2004, during the take-off roll on runway 34 Left at Sydney Kingsford Smith Airport, they felt shuddering from the nose wheel. The crew of a subsequent landing aircraft reported debris on the runway. An inspection found tyre segments and pieces of aircraft structure. The 737 crew were notified and elected to return for a landing.

An investigation by the operator found that the 737 struck a Boeing 747 thrust reverser blocker door that had fallen from an aircraft that had previously used the runway. That door damaged the 737 nose landing gear tyre and gashed the aluminium skin of the fuselage. The investigation was unable to identify the 747 and whether the loss of the door occurred during take-off or landing.

This was the second reported occurrence of a blocker door falling from a 747 aircraft. At least two 747 operators (one Australian and one international) are known to have found that an earlier 747 blocker door modification had a deficient metal/composite bond. The Australian 747 operator has initiated a project to scope and implement a new modification program to repair or replace all blocker doors.

Occurrence summary

Investigation number 200401756
Occurrence date 15/05/2004
Location Sydney, Aero.
State New South Wales
Report release date 30/06/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Foreign object damage / debris
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 737
Registration VH-TAH
Serial number 23479
Sector Jet
Operation type Air Transport High Capacity
Departure point Sydeny, NSW
Destination Cairns, QLD
Damage Minor

Aircraft details

Manufacturer The Boeing Company
Model 747
Sector Jet
Operation type Air Transport High Capacity
Departure point Unknown
Destination Unknown
Damage Minor

Piper PA-32R-301, VH-WMC

Summary

The Australian Transport Safety Bureau did not conduct an on scene investigation of this occurrence. The report presented below was derived from information supplied to the Bureau.

The Piper PA 32R-301 aircraft, registered VH-WMC, was intended to be flown on a return charter flight from Winton to Boulia in Queensland. The flight was to familiarise the pilot in command with the route and the facilities at Boulia Aerodrome. The aircraft load, which comprised 300 litres of fuel and six adults, including the pilot in command and the aircraft owner, placed the aircraft approximately 67 kg above the maximum allowable take-off weight. The weather was bright and clear with a light easterly wind, and an ambient temperature of approximately 15 degrees C.

The pilot in command reported that all pre-flight checks and engine indications were normal, and that the elevator trim was set rearward of the neutral position, in accordance with the Aircraft Operating Manual. One stage of flap was selected and they were using runway 14 at Winton. The initial take-off roll was normal and rotation was initiated at about 80 knots. The pilot reported that the aircraft became airborne and then veered to the left of the runway centreline. The pilot lowered the nose of the aircraft slightly in an attempt to gain airspeed and increase aircraft control, but it veered right and travelled beyond the edge of the runway towards the aerodrome boundary fence. Throughout this period, the aircraft became airborne but did not fly out of ground effect. In a further attempt to increase speed, the pilot retracted the landing gear. However, the aircraft settled onto its lower fuselage and collided with the aerodrome boundary fence.

On the day before the accident, the pilot in command completed three circuits as a refamiliarisation exercise in the aircraft type. The aircraft owner, also a pilot, accompanied the pilot in command and occupied the right cockpit seat. No other persons were on board the aircraft. At the owner's suggestion, the pilot in command set the elevator trim close to the full forward position before takeoff. The owner reported that the pilot in command handled the aircraft satisfactorily.

The Aircraft Operating Manual stated that for a normal takeoff, the elevator trim should be set slightly rearward of neutral, and that the aircraft should be accelerated to 74 to 80 knots, depending on its weight, before backpressure on the control wheel was applied to rotate the aircraft to the climb attitude. From the information provided, it is likely that a combination of the different trim setting, the rear centre of gravity position, and the higher aircraft weight for the accident takeoff, compared with the flight the previous day, resulted in the aircraft assuming a high nose-up attitude after becoming airborne. The resultant drag lead to the control difficulties reported by the pilot and prevented the aircraft accelerating to the normal climb speed.

Occurrence summary

Investigation number 200401661
Occurrence date 11/05/2004
Location Winton, Aero.
State Queensland
Report release date 04/08/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Piper Aircraft Corp
Model PA-32
Registration VH-WMC
Serial number 32R-8013036
Sector Piston
Operation type Charter
Departure point Winton, QLD
Destination Boulia, QLD
Damage Substantial

de Havilland Canada DHC-8-102, VH-TQQ

Summary

The de Havilland DHC-8 (Dash 8) aircraft, registered VH-TQQ, departed Mildura, Victoria, and was within the mandatory broadcast zone (MBZ), on climb to its cruising level, when it came into conflict with a Cessna Aircraft Company 150G (Cessna) aircraft, registered VH-KXF.

The Australian Transport Safety Bureau did not conduct an on-scene investigation of this occurrence.

Occurrence summary

Investigation number 200401411
Occurrence date 19/04/2004
Location 13 km SE Mildura, Aero.
State Victoria
Report release date 17/12/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Separation issue
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer De Havilland Canada/De Havilland Aircraft of Canada
Model DHC-8
Registration VH-TQQ
Serial number 204
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Mildura, VIC
Destination Melbourne, VIC
Damage Nil

Aircraft details

Manufacturer Cessna Aircraft Company
Model 150
Registration VH-KXF
Serial number 15066535
Operation type Flying Training
Departure point Swan Hill, VIC
Destination Kulinine, VIC
Damage Nil

Boeing 737-7BX, VH-VBT and Lancair IV-P, VH-LDJ, 93 km north-west of Brisbane Airport, Queensland, on 7 April 2004

Safety Action

As a result of this and other occurrences, Airservices Australia has:

  • issued National Instruction NI 09/2004, Safety Alerts, Traffic Avoidance Advice and Traffic Information;
  • issued to all holders of the Aeronautical Information Publication, Aeronautical Information Circular H10/04, Traffic Information - Safety Alerts, dated 2 Sep 04;
  • produced a computer-based training program for ATS controllers on duty of care, which provides guidance on when a safety alert is required to be initiated.

Related Documents: | Media Release |

Analysis

Throughout this analysis it should be noted that the pilots of both aircraft and the ATS controller involved in the occurrence complied with the rules and procedures for operation in Class E airspace associated with the NAS phase 2b, implemented on 27 November 2003.

The regulations, procedures and educational material associated with that implementation stated that there was a shared responsibility by pilots of IFR and VFR flights to see-and-avoid each other in Class E airspace.

Prior to the implementation of NAS phase 2b on 27 November 2003, both aircraft involved in this occurrence would have been operating in Class C airspace. As such, they would have been subject to an ATS airways clearance and would have been provided with separation in accordance with Class C airspace rules and procedures. In order for two aircraft to pass in close proximity at these flight levels in Class C airspace, those rules and procedures would need to have been compromised. As the pilots of both aircraft and the ATS controller complied with the rules and procedures for Class E airspace under NAS, those rules and procedures do not preclude an IFR high performance, high-capacity regular public transport aircraft from passing within such close proximity as to generate a TCAS RA on either known or unknown VFR traffic.

The controller's relatively low workload and other factors, such as the Lancair pilot submitting flight notification details, and broadcasting his departure from Maroochydore, assisted the ATS controller to detect a possible conflict. Although there was no requirement for the controller to pass traffic information to the pilot of the Lancair about the location of the 737 under NAS Class E airspace procedures, the controller provided traffic information to both aircraft with respect to each other.

Part 5 of MATS also stated that controllers shall issue a safety alert when, in the consideration of the controller, such an advice was warranted to avoid conflict. In the circumstances of this occurrence, the controller had provided traffic information to the crews of both aircraft, and the Lancair pilot had broadcast that he had the 737 in sight. Accordingly, the onus was then on the Lancair pilot to avoid the 737. In those circumstances, the provision of a safety alert, which may have included a suggested course of action, may also have complicated the situation, if that suggestion was contrary to what the pilots of each aircraft considered necessary.

Provision of a safety alert, in the circumstances of this occurrence, was not required. However, MATS did not provide any guidance to controllers on the circumstances under which the provision of a safety alert would be appropriate. Publication of those guidelines may assist controllers to determine when a safety alert should be issued.

In Class E airspace, the provisions of CAR 163A required the crews of both aircraft to 'see and avoid' each other. The 737 crew were unable to see the Lancair despite their attempts to do so. The Lancair pilot reported that he had the 737 in sight. When the 737 crew observed the position of the Lancair on the TCAS navigation display, they commenced action to avoid a confliction prior to receipt of both the TCAS TA and RA. In concert with that action, they continued in their attempts to visually acquire the Lancair, in accordance with Class E airspace see-and-avoid requirements.

In the circumstances of this occurrence:

  • the ATS controller took more actions than those required by the published requirements for Class E airspace and MATS;
  • the Lancair pilot took more actions than those required by the published procedures for Class E airspace under NAS;
  • the early action taken by the 737 crew to avoid the conflict was not contrary to the published procedures for Class E airspace under NAS.

Despite those actions, the two aircraft came into such proximity that a TCAS RA was generated in the 737.

Both aircraft were operating in Class E airspace that was introduced as part of the National Airspace System (NAS) phase 2b on 27 November 2003. (An ATSB research report titled National Airspace System Stage 2b: Analysis of Available Data was released in July 2004.) As no prescribed separation standards are applicable in these circumstances, there was no infringement of separation standards. However, ATS audio tapes, radar and TCAS data, and information obtained from the air traffic controller and the pilots of both aircraft were consistent and indicate that the aircraft came into such close proximity that a threat to the safety of the aircraft may have existed. Therefore, the incident has been classified by the ATSB as an airprox event.

The incident at Canty IFR reporting point, on 3 December 2003 (ATSB report 200304963) was also classified as an airprox event.

Unlike this incident north of Brisbane on 7 April 2004 and the Canty incident, the occurrence near Launceston on 24 December 2003 (ATSB report 200305235) was classified as a serious incident due to the lack of radar coverage in the Launceston area and the absence of radio broadcasts from the pilot of the Tobago, which created an unalerted see-and-avoid environment for the crew of the Boeing 737. The air traffic controller also was unaware of the Tobago.

Summary

On 7 April 2004, a Boeing 737-7BX (737) aircraft registered VH-VBT, operating under the instrument flight rules (IFR), was en route from Townsville and descending for a landing at Brisbane. A Neico Lancair IV-P aircraft registered VH-LDJ, operating under the visual flight rules (VFR), was en route from Maroochydore to St George, on climb to flight level (FL) 1651. Both aircraft were operating in radar Class E airspace at the time of the occurrence.

The Lancair pilot reported to the Air Traffic Services (ATS) controller that he had departed Maroochydore at 0718 Eastern Standard Time2, although in accordance with the National Airspace System (NAS) procedures, there was no requirement for him to do so3. The controller issued the Lancair pilot with a discrete transponder code to assist with his situational awareness. Published NAS procedures stated that:

In Class E airspace, IFR and VFR flights are permitted. IFR flights are provided with an air traffic control service, are separated from other IFR flights, and receive traffic information on VFR flights as far as is practicable. VFR flights receive a Radar Information Service (RIS)4 on request.5

Those procedures also stated that, for VFR aircraft operating in Class E airspace, '…no flight notification was required…' and pilots of aircraft conducting operations under the VFR were required to monitor the appropriate radio frequency. The Lancair pilot submitted flight notification details to ATS prior to departure from Maroochydore, and reported that departure to ATS.

In accordance with those procedures, the controller was not providing traffic separation6 to either aircraft, and advised the 737 crew accordingly. Recorded ATS audio information showed that the controller provided traffic information about the Lancair to the 737 crew on three occasions between 0721:58 and 0725:08. At 0722:17, and again at 0725:38, the controller provided the Lancair pilot with traffic information about the 737, although there was no requirement for him to do so in Class E airspace. During the first transmission at 0722:17, the controller advised the Lancair pilot that the 737 was crossing traffic which would pass in about 15 NM and was on descent into Brisbane. During the second transmission at 0725:38, the controller advised the Lancair pilot that the 737 was 'in your 2 o'clock at 8 miles now'. ATS radar data showed that, at 0725:38, the 737 was 8.8 NM from the Lancair. At 0725:47, in response to that broadcast, the Lancair pilot advised the controller that he had the 737 in sight.

As the 737 was passing through about FL157 at 0726:01, the crew reported that they observed a traffic alert and collision avoidance system (TCAS)7 traffic symbol on the aircraft's navigation display, about the Lancair. They attempted to visually acquire the Lancair, but were unable to see that aircraft. Recorded data from the 737's flight data recorder (FDR) showed that, at that point, the crew commenced manoeuvring the aircraft by reducing the rate of descent. At about 0726:18, the crew received a TCAS traffic advisory (TA)8. The crew reported that they were still unable to visually acquire the Lancair and were uncertain of its relative position. Recorded FDR data indicated that at 0726:34, the crew disengaged the autopilot and commenced a right turn away from the Lancair. They subsequently levelled the 737 at FL153 and then climbed to FL154. At 0726:40 and at 15,420 ft the 737 received a TCAS resolution advisory (RA)9 aural warning instructing them to climb, in response to the proximity of the Lancair. They subsequently climbed the 737 to FL166 and continued the turn to about 15 degrees right of track. The duration of the RA was 10 seconds and commenced when the Lancair was about 650 ft vertically lower and about 0.7 NM to the left of the 737.10 Recorded ATS radar data showed that, at about 0726:45, the Lancair altered track 8 degrees to the right away from the 737, just before passing behind and below the 737. The Lancair pilot reported that he did not experience the effect of wake turbulence from the 737. The minimum distance between the two aircraft was about 600 ft vertically at about 0.3 NM laterally.11

The Class E airspace in which the 737 and the Lancair were operating at the time of the occurrence was introduced as part of NAS phase 2b on 27 November 2003. Prior to NAS phase 2b, that volume of airspace was classified as Class C airspace. In Class C airspace, both aircraft would have been subject to an ATS airways clearance and would have been separated in accordance with prescribed standards.

In Class E airspace, the pilots of aircraft operating under the IFR and VFR were required to:

…maintain vigilance so as to see, and avoid other aircraft.12

The NAS Implementation Group reference guide, distributed as part of the NAS phase 2b implementation, stated that:

The other important change is that the pilot of a VFR flight should not make broadcasts on ATC frequencies.13

It also stated that:

Pilots of VFR flights may monitor the ATC frequency to enhance situational awareness.

Please do not make broadcast transmissions or engage in chatter on an ATC frequency. The safety of others depends on you not doing this.

Pilots are not precluded from responding to any ATC or pilot transmission when they believe their safety is at risk from another aircraft.

Part 2, Section 2, paragraph 2.2.4.1 of the Manual of Air Traffic Services (MATS) stated that:

Before providing a radar service to an aircraft, radar identification shall be established.

Although the controller did not advise the Lancair pilot that the Lancair was radar identified, the controller issued a discrete transponder code to the Lancair pilot and radar-identified the aircraft before providing a Radar Information Service to the pilot.

Part 4, Section 1, paragraph 4.1.1.1 of MATS contained information regarding ATS controller responsibilities for providing aircraft separation. The manual stated that:

Separation shall be provided by ATC using approved separation standards and procedures.

In the circumstances of this occurrence, the ATS controller was not required to provide separation to either aircraft in respect of the other and there were no separation standards applicable in these circumstances in Class E airspace.

Part 4, Section 1, paragraph 4.1.1.3 of MATS stated that:

Nothing in this chapter precludes a controller from using discretion and initiative in any particular circumstance where these procedures appear to be in conflict with the requirement to promote the safe conduct of flight.

In the circumstances of this occurrence, the ATS controller provided traffic information to the crews of both aircraft in respect of the other, although under NAS procedures there was no requirement for him to provide traffic information to the pilot of the Lancair on the location of the 737.

Part 5, Section 1, paragraph 5.1.13 of MATS provided information regarding provision of safety alerts. Paragraph 5.1.13.1 stated that:

A safety alert shall be issued to an aircraft when a controller is aware the aircraft is in a situation which is considered to place it in unsafe proximity to terrain, obstructions, or other aircraft.

The controller reported that, once the Lancair pilot broadcast that he had the 737 in sight, there was no necessity to broadcast a safety alert to either the Lancair pilot or the 737 crew. The controller also reported that if that pilot had not broadcast that he had the 737 in sight, his next option was to issue a safety alert. MATS did not provide any guidance to controllers on what might be considered '…unsafe proximity…', or when to issue a safety alert.

The NAS Implementation Group reference guide contained information for VFR pilots regarding separation from other aircraft when operating in Class E airspace. Page 16 of that guide stated that:

When you are flying in Class E airspace you are responsible for separation from other aircraft. The onus is on you to look out and see and avoid other aircraft.

Part 12, The Rules of the Air, Division 1, of the Civil Aviation Regulations (CAR) 1988, contained information regarding right of way, prevention of collision, operating near other aircraft and responsibilities of flight crew to see and avoid aircraft. More specifically, CAR 161 contained information regarding right of way and stated that:

(1) An aircraft that is required by the rules in this Division to keep out of the way of another aircraft shall avoid passing over or under the other, or crossing ahead of it, unless passing well clear.14

(2) The pilot in command of an aircraft that has the right of way must maintain its heading and speed, but nothing in the rules in this Division shall relieve the pilot in command of an aircraft from the responsibility of taking such action as will best avert collision.

CAR 162 (1) contained information regarding prevention of collision and stated that:

When 2 aircraft are on converging headings at approximately the same height, the aircraft that has the other on its right shall give way…

Although not specifically referring to converging aircraft, CAR 162 also stated that '…each shall alter its heading to the right…', and when referring to the aircraft other than the aircraft having right of way, '…shall keep out of the way of the other aircraft by altering its heading to the right…'.


CAR 163 (1) contained information regarding operating near other aircraft and stated that:

The pilot in command of an aircraft must not fly the aircraft so close to another aircraft as to create a collision hazard.

The 737 was on the Lancair's right and, in accordance with CAR 161 and CAR 162 (1), had right of way. The Lancair pilot reported that he had the 737 in sight. While the crew of the 737 had observed a traffic symbol on the TCAS display, they reported that they did not see the Lancair, despite attempts to do so.

Information obtained from the crews of both aircraft, the ATS controller, recorded flight data from the 737, ATS audio recordings and radar data, was consistent and indicated that the crews of both aircraft and the ATS controller complied with the published procedures for Class E airspace under NAS.

Based on the factual data, and the definition contained in Regulation 2.2 of the Transport Safety Investigation Regulations 2003, the incident was classified as an airprox event.15

1 16,500 ft with an altimeter pressure sub-scale setting (QNH) of 1013.2 hPa.
2 The 24-hour clock is used in this report to describe the local time of day, Eastern Standard Time (EST), as particular events occurred. Eastern Standard Time was Coordinated Universal Time (UTC) + 10 hours.
3 Aeronautical Information Publication (AIP), ENR 1.1, Sections 3.4 and 18.3.2.
4 Radar Information Service (RIS) is defined in Part 10, Section 1 of the Manual of Air Traffic Services as:

An add-on ATC service within radar coverage, which provides information to flights, not otherwise receiving a separation service, in order to improve situational awareness, and assist pilots in avoiding collisions with other aircraft.


5 AIP, ENR 1.4, Section 2.1.4 and pages 12-13 and 40 of the NAS Implementation Group Reference Guide - How to Operate in the National Airspace System, effective from 27 Nov 2003.
6 Separation is defined in Part 10, Section 1 of the Manual of Air Traffic Services as:

A controlled condition using defined standards to prevent collisions between aircraft.

7 The Boeing 737-NG Operations Manual, Volume 2, states that:
 

TCAS alerts the crew to possible conflicting traffic. TCAS interrogates operating transponders in other airplanes, tracks the other airplanes by analysing the transponder replies, and predicts the flight paths and positions. TCAS provides advisory, flight path guidance, and traffic displays of the other airplanes to the flight crew. Neither advisory, guidance, nor traffic display is provided for other airplanes which do not have operating transponders. TCAS operation is independent of ground-based air traffic control.

8 A traffic advisory (TA) is generated when the other aircraft is approximately 40 seconds from the point of closest approach, dependent upon aircraft altitude.
9 If the other aircraft continues to close, a resolution advisory (RA) is generated when the other aircraft is approximately 25 seconds from the point of closest approach, dependent upon aircraft altitude. The RA provides aural warning and guidance as well as manoeuvre guidance to maintain or increase separation from the traffic.
10 The recorded ATS radar data and the 737 flight recorder data was consistent. However, the accuracy of that information is dependent upon the tolerances associated with both aircraft altimeters and the ATS radar equipment.
11 The horizontal distance was determined using the radar positions that were recorded every 5 seconds. By interpolating between those points to derive a position every second, the minimum horizontal separation was 0.3 NM, dependent upon the tolerances previously mentioned.
12 Civil Aviation Regulations 1988, 163A - Responsibility of flight crew to see and avoid aircraft.
13 Page 8 of the NAS Implementation Group Reference Guide - How to Operate in the National Airspace System, effective from 27 Nov 2003.
14 The investigation was unable to locate a CAR definition of '…well clear…'.
15 An airprox event is defined in Regulation 2.2 of the Transport Safety Investigation Regulations 2003, as:

…an occurrence in which 2 or more aircraft come into such close proximity that a threat to the safety of the aircraft exists or may exist, in airspace where the aircraft are not subject to an air traffic separation standard or where separation is a pilot responsibility.

Occurrence summary

Investigation number 200401273
Occurrence date 07/04/2004
Location 93 km NW Brisbane, Airport
State Queensland
Report release date 21/10/2004
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Separation issue
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 737
Registration VH-VBT
Sector Jet
Operation type Air Transport High Capacity
Departure point Townsville, QLD
Destination Brisbane, QLD
Damage Nil

Aircraft details

Manufacturer Neico Aviation Inc
Model Lancair IV-P
Registration VH-LDJ
Serial number 138
Sector Piston
Operation type Private
Departure point Maroochydore, QLD
Destination St George, QLD
Damage Nil