On 3 November 2015, at about 1400 Western Standard Time (WST), a pilot of a Eurocopter AS365 N3 (Dauphin), registered VH-WPX, conducted a maintenance test flight at Jandakot Airport, Western Australia.
The test flight was the third that day, to conduct track and balancing of the main rotor, following reports of vibration.
During the post-flight inspection following this test flight, one of two Licenced Aircraft Maintenance Engineers (LAMEs) involved in the test flight, noticed two large gouges to the leading edge of one of the main rotor blades (Figure 1).
A spanner that had been used during the third track and balance related adjustments could not be located. It was later located on an adjacent taxiway about 43 m from the hangar. Due to the scuff marks and scratches found on the spanner, it was determined that it had been left in the rotor head area and was likely ejected during the aircraft start up.
Figure 1: Damage to leading edge of a main rotor blade on VH-WPX
Source: Aircraft operator
Events leading up to the foreign object damage
Prior to the event, the main rotor head bolts (bolts) had approached their scheduled life limit. So on 26 October the maintenance organisation replaced the bolts, in accordance with the Airbus Helicopters AS365[1] Maintenance Manual. The maintenance manual required that a main rotor blade track and balance be performed following this replacement.
Helicopter vibration was automatically monitored using the Honeywell Chadwick Helmuth Vibration Expert (VXP), which was installed in the helicopter. The VXP data generated was automatically sent to an external diagnostics organisation for trend monitoring. Additionally, LAMEs could access this data for rotor track and balancing requirements.
The operator advised that when the bolts were replaced, a work pack[2] was generated for the task.[3] Prior to the required track and balancing flights, one of the two LAMEs tasked with the job (LAME 2), transferred the main rotor blade track and balancing procedure to the aircraft technical log[4] and ground run/test flight sheet.[5]
However, due to non-availability of flight crew, the test flights were not conducted until 28 October. The ground run/test flight record indicated that the results of the track and balance procedure were satisfactory, and the aircraft was returned to service the same day.
The aircraft continued in service, and flew about 14 hours between 28 October and 3 November. During this period, the maintenance organisation reported that a 4P vibration[6] (within manufacturer tolerance) was being monitored and a pilot advised of a vibration. However, this information was not formally recorded on technical documentation.
On 2 November, the external diagnostics company that monitored the aircraft VXP data, advised the operator of a rising vibration trend. This rising vibration trend was still within tolerance, and supported the pilot reported vibration that was being monitored by the maintenance engineers. At this time, the Chief Engineer advised the other LAME (LAME 1) to conduct further main rotor track and balancing during the following few days, subject to pilot availability.
Further track and balancing, and smoothing, was conducted on 3 November. The two LAMEs’ recollections and observations of the task are detailed below.
LAME 1
Reported that a work pack had not been created for the subsequent track and balancing job, however, they (LAME 1) endorsed the ground run/test flight sheet and annotated the corresponding number on the technical log prior to the test flights.
Reported that the Chief Engineer had discussed the required maintenance with them.
Reported that although not formally assigned the role, thought they were most likely the Job Coordinator.
LAME 1 had tagged out a socket and a screwdriver. Prior to each test flight, LAME 1 placed the tools being used into a metal tray, and then placed the tray on top of the toolbox. As the job was ongoing, there had been no documented requirement to place the tools back into their assigned location. LAME 1 had visually checked the tools in the metal tray prior to the third test flight, but did not use the tag procedure (refer Tool Control Procedure).
LAME 1 had performed adjustments to the main rotor pitch links and blade weights, and had asked LAME 2 to perform an independent inspection[7] of the work after the second test flight. LAME 1 reported that the request had been for LAME 2 to both perform the independent inspection, and to check that no tools had been left on the helicopter.
LAME 1 was not aware that the spanner that they had been using had been left on top of the main rotor blades.
LAME 2
Also reported that a work pack had not been created for the job.
Stated that prior to the third test flight, they (LAME 2) had completed an independent inspection of the maintenance tasks, performed by LAME 1.
LAME 2 did not notice that the spanner had been left on top of a main rotor blade. They noted that the blade was very flat, and that it would not be possible to see it on top of the rotor blade from the ground.
LAME 2 had tagged the spanner and several other tools out earlier in the day. The tools had not been returned to the toolbox during the day, as it was expected that further adjustments would be required.
Pre-flight inspection
The daily inspection had been certified in the aircraft technical log by an engineer prior to the first flight. Additionally, the pilot reported conducting a ‘walk-around inspection’ in accordance with the flight manual procedures. The pilot was aware that flight control maintenance had been conducted by the engineering group. The pilot signed the aircraft technical log and ‘accepted’ the aircraft prior to each of the three test flights.
The pilot reported that the aircraft handled normally throughout the three test flights.
Tool control procedure
While there was a practice of tool control in place prior to the incident, formal procedures had not been documented and incorporated in the maintenance organisation manual (MOM).
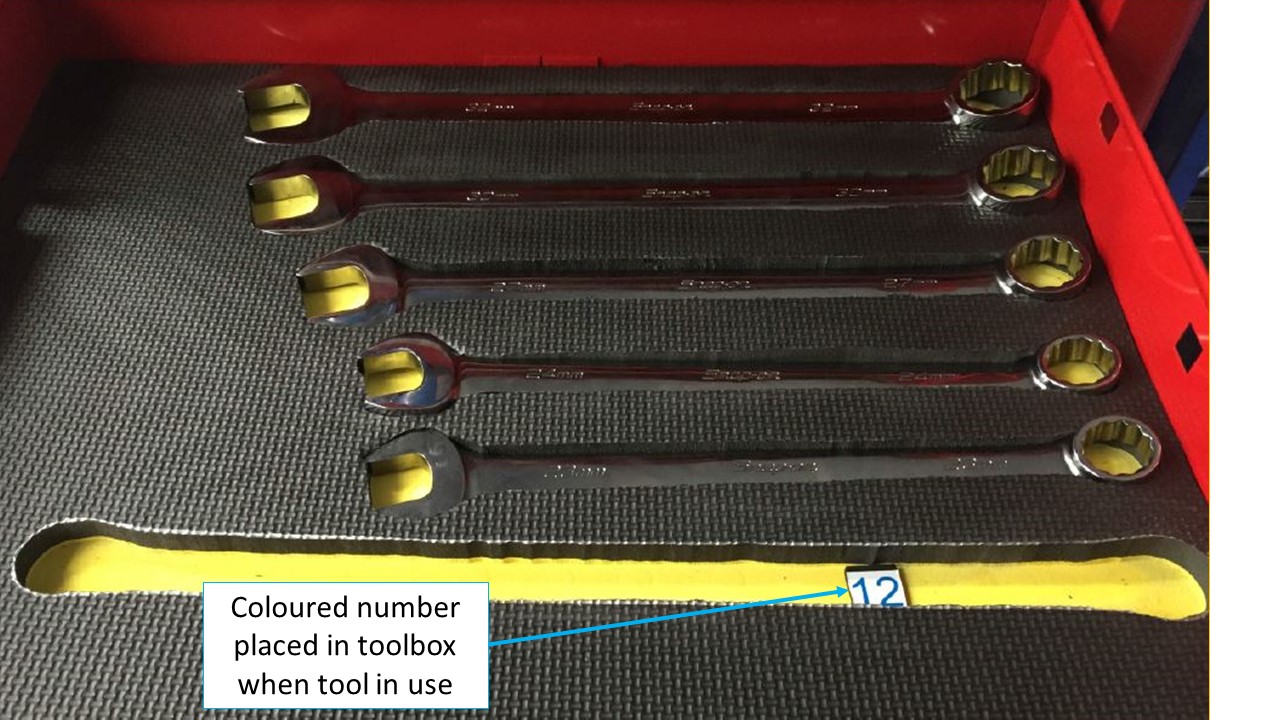
The tool control practice in place, prior to this incident, required that that each tool removed from the toolbox be tagged out by the person removing the tool. Each engineer was assigned a series of numbered tags of a certain colour, and the tag was placed into the ‘empty’ location (cut out) of the tool being used (Figure 2). A review of both the toolbox and the engineer’s assigned tags would quickly identify if any tools were still in use.
Figure 2: Tool control procedure showing coloured number replacing tool in use by the engineer assigned the blue coloured tags
Source: Operator
Operator procedures
The MOM stated that induction training of all staff shall be carried out on all new maintenance staff. This training was to provide staff with sufficient information to enable them to integrate into the company and to ensure compliance with the policies and procedures of the organisation. However, there was no written record of any such induction training having taken place.
ATSB comment
The organisation involved conducted a thorough internal investigation after this occurrence. There were a range of other issues identified in regard to training and documentation procedures, and the company have initiated remedial action in all these areas. These other issues do not fall within the scope of this investigation.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
The operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:
Tool control procedure
A tool control procedure was in place at the time of the incident, however, the procedure had not been documented in the MOM. Additionally, there was no documented procedure requiring the tools to be returned to the toolbox prior to the aircraft being started.
The operator will incorporate the tool control procedure into the MOM. This procedure requires that all tools used during any aircraft maintenance are returned to the tool storage location prior to any of the company aircraft being started.
A tool control procedure will be implemented for any maintenance that occurs away from the main base. Additionally, a tool control procedure will be implemented to ensure external maintenance providers (for example avionics specialists) adopt the company tool control procedure.
Training for maintenance personnel
All maintenance personnel be provided with sufficient training and information to enable them to understand the workings of the organisation, its policies, manuals, procedures and their individual responsibilities.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 29 October 2015, a pilot who held a restricted pilot licence, and a flight instructor, prepared for a training flight at Camden Airport, New South Wales. The plan was to conduct circuits at Camden, in a Liberty XL-2 aircraft, registered VH-CZS (CZS). The pilot conducted a pre-flight inspection of the aircraft, with no defects found.
At about 1140 Eastern Daylight-saving Time (EDT), after the pilot had completed the normal pre-flight checks, and received the required air traffic control clearances, the aircraft took off for the first circuit. The pilot completed two normal circuits with touch-and-go landings on runway 06, and climbed out on runway heading for the third circuit.
During the initial climb, the pilot felt backward pressure on the control stick, and selected the electric pitch trim to a slightly nose down position. The aircraft was then in a stable climb, at an airspeed of 75 to 80 kt. As the aircraft passed about 500 ft above mean sea level (AMSL), the pilot retracted the flaps.
Passing about 700 ft, the pilot commenced a climbing turn onto the downwind leg. As the pilot rolled the wings level on downwind, the aircraft was still about 100 ft below the circuit altitude of 1,300 ft AMSL. The pilot therefore continued a shallow climb with the wings level, at an airspeed of about 95 kt. Suddenly, the control stick came back towards the pilot, and the aircraft pitched to a nose-up attitude.
The pilot pushed forward on the stick with both hands, to a full forward position. They also asked the instructor to adjust the pitch trim to a more nose-down position, to try to return the aircraft to a level attitude. The pilot stated there was something wrong and handed control of the aircraft to the instructor, who also assessed that there was a control issue. The aircraft descended rapidly in a nose-up attitude, and the aircraft then pitched nose-down.
The aircraft descended to about 700 ft, and the pilot broadcast a Mayday[1] to the Camden tower controller advising them of a control issue. The controller asked whether they could make it back to land on runway 06, and the pilot replied ‘negative’. The pilot and instructor elected to conduct a precautionary landing in a paddock ahead of the aircraft. The instructor sighted powerlines and overflew them before extending full flap and landing in the paddock.
During the landing roll, the aircraft collided with two fences and came to rest in a stand of trees. The pilot and instructor were uninjured, and the aircraft sustained substantial damage (Figure 1).
Engineering inspection
An engineer conducted a post-accident inspection of the aircraft, and did not find any obvious defect that may have contributed to the control issue.
Figure 1: Accident site
Source: Insurance assessor
Pilot comments
The pilot and instructor provided the following comments:
Once they had moved the trim to the full nose-down position, the instructor elected to leave it there and not try to move it, in case it made controlling the aircraft more difficult.
The pilot initially assessed there was a problem with the stabilator, as it felt as if something had jammed in it.
They assessed that it was preferable to land with a slight tailwind in the paddock, than to attempt to turn the aircraft and land into wind.
At the commencement of the flight, the aircraft was about 20 kg below the maximum take-off weight and within the normal centre of gravity range.
The aircraft flight manual included a checklist for partial control failure or malfunction, but they did not have sufficient time to access the manual during the incident. The checklist advised the pilot to check the trim setting and the circuit breakers, to control the aircraft with power and whichever controls were operational, and to land as soon as possible. The instructor also stated that they did not have time to check the circuit breakers, which were on the right side of the instrument panel.
The instructor reported that as well as the pitch, or elevator, control issue, the aileron, or roll control felt overly sensitive. When the instructor applied light pressure to roll the aircraft to the left, it was overly responsive. This influenced the decision to land in the paddock ahead, rather than attempt to turn the aircraft into wind or to return to land on the runway.
Operator comments
The operator assessed that the way the pilots used the trim may have led to the control difficulties.
Safety message
The pilot and instructor both commented that their communication during the incident was very good, and that played a key role in getting the aircraft safely to the ground. Faced with an abnormal situation, the pilots communicated effectively, and collaborated to share the workload.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 21 October 2015, a Gippsland Aeronautics GA-8 aircraft, registered VH-FGN (FGN), was conducting parachute operations at Busselton Airport, Western Australia (Figure 1). Prior to commencing the day’s operations, a company pilot conducted a pre-flight inspection of the aircraft, with no defects found.
Figure 1: VH-FGN
Source: Aircraft operator
At about 1500 Western Standard Time (WST), FGN took off from Busselton Airport with a pilot and seven parachutists on board. As the aircraft climbed through about 2,000 ft, the pilot observed a decrease in the engine manifold pressure. The manifold pressure was still in the green arc, or normal operating range, but indicating about 30 inches. The normal manifold pressure during the climb was about 38 inches. The fuel flow also increased from about 120 L/hr to 154 L/hr. As the aircraft was tracking south towards forested terrain, the pilot elected to turn back towards the aerodrome, and continue the climb, in case the engine issue worsened. The pilot conducted the standard engine checks, but the engine continued to produce only partial power. The pilot broadcast a Mayday[1] on the Melbourne Centre air traffic control (ATC) frequency.
The pilot advised the parachutists that they would establish the aircraft in the drop run overhead the aerodrome at about 4,000 ft (instead of the planned FL 140[2]) to allow the parachutists to exit the aircraft. As the pilot subsequently reduced engine power to allow the parachutists to exit the aircraft, the engine ran roughly. Six of the parachutists exited normally and landed safely at the drop zone, while the seventh, who was also a company pilot and seated in the front passenger seat, remained in the aircraft with the pilot in command.
The pilot then increased the aircraft’s power until the engine ran smoothly, although only producing partial power, while continuing the descent to the aerodrome. The pilot also advised ATC that they did not require immediate assistance and downgraded to a PAN[3], as the engine continued to produce some power. The aircraft landed safely at Busselton at about 1514.
After shutting down the engine, the pilot consulted with the maintainer, and found that the intake tube on the No. 4 cylinder was loose.
Aircraft maintenance and engineering inspection
On 10 October 2015, a licensed aircraft maintenance engineer had completed a 100-hourly inspection on the aircraft, including a ‘top overhaul’ of the engine.
After the incident, the engineer completed the following:
removed the bolts and inspected the wire thread (Helicoil) inserts, and found no damage
fitted a new intake gasket and o-ring to the intake tube, and resecured the tube to the No. 4 cylinder with new spring washers
checked the torque of all other intake tube bolts, and found none loose.
Safety message
This incident highlights the importance of having thoroughly rehearsed emergency procedures, particularly for parachute operations. The parachutists had, in accordance with standard procedures, removed the single point restraints during the climb, and were prepared to exit the aircraft quickly.
For pilots, this provides a reminder that constant monitoring of the engine instruments can provide early indication of a problem. Acting quickly on this information may reduce the impact of partial or total power loss on flight safety.
The ATSB publication Avoidable Accidents No. 3 – Managing partial power loss after take-off in single-engine aircraft, provides information also relevant to partial losses of power in flight as well as after take-off. Following a complete engine failure, a forced landing is inevitable. For a partial power loss, pilots are faced with deciding whether to continue the flight or land immediately.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 10 September 2015, at about 0930 Eastern Standard Time (EST), an instructor and student pilot of a Cessna 172M aircraft, registered VH-EJM (EJM), were conducting circuits at Townsville Airport, Queensland.
The student was flying the aircraft and on mid-final for a touch-and-go landing on runway 07, when the instructor noticed a truck on the perimeter road, near the threshold to runway 07. The truck had not held at the stop sign. The stop sign required all vehicles to stop, look for aircraft, and not proceed unless there was no aircraft landing (Figure 1).
Shortly after the instructor sighted the truck, the Townsville Tower air traffic controller advised the pilots of EJM that there was a truck on the perimeter road. The instructor acknowledged the controller and they proceeded with the landing.
The aircraft conducted a touch-and-go and continued with several more circuits without incident.
Figure 1: Townsville airport perimeter road near runway 07
Source: Google earth, modified by the ATSB
Instructor and aircraft operator comments
The instructor commented that another vehicle on the perimeter road, ahead of the truck, also did not stop at the stop sign.
The operator reported this could potentially have been a more serious issue if the student pilot was conducting their first solo flight, as there would be greater risk that the student might get low on the approach and might not see the truck.
Department of Defence investigation
The Department of Defence conducted an investigation into the serious incident. They determined that a contractor, driving a truck on the western perimeter road, failed to stop at the stop sign near the threshold of runway 07. VH-EJM missed the top of the truck by about 4 to 5 metres and the aircraft landed without incident.
The Department of Defence also conducted a subsequent investigation into an incident where a contractor driving a truck on the western perimeter road failed to stop at the stop sign near the threshold of runway 07. The pilot of a Cessna C172RG aircraft that was on short final, saw the truck coming towards their approach path and informed air traffic control. Air traffic control acknowledged the transmission. The truck stopped almost directly under the path of the arriving aircraft and the aircraft landed without incident.
The investigation determined that the stop signs located on the perimeter road on approach to runway 07 provided drivers with clear direction to stop, observe and give way to approaching aircraft. The failure of the drivers of the vehicles in these incidents to observe those protocols created the potential for a collision between the vehicle and the aircraft.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Department of Defence
As a result of this occurrence, the airport operator has advised the ATSB that they are taking the following safety actions:
briefing material for contractors has been updated placing greater emphasis on safety around runways.
flashing lights have been installed on the stop signs, for the under-run service road, to improve observation of the sign by drivers.
ATSB comment
At the time of writing this report, two other similar events occurred on 8 and 10 December 2015. The occurrences were subsequent to the update of briefing material for contractors and the installation of flashing lights on the stop signs. The Department of Defence are conducting a review of their safety actions to see if there are any other options to prevent a re-occurrence.
Safety message
The International Civil Aviation Organization (ICAO) has identified runway safety as one of its priorities and has been working with countries and aviation organisations globally to reduce runway safety accidents. ICAO has developed a runway safety website, which offers a range of information and products to assist the aviation community to improve runway safety.
In addition, ICAO has published a Manual on the Prevention of Runway Incursions Doc 9870 AN/463, available from the ICAO website. The manual includes information on the prevention of runway incursions. The manual discusses that deficiencies in design, training, technology, procedures, regulations and human performance can result in a system break down and safety being compromised. A pilot, as part of the last line of defence, cannot assume that anyone will do the right thing, like the driver of the truck stopping at the stop sign, and they need to be prepared to re-evaluate the planned flight.
Additional information on runway safety is also available from the Airservices Australia webpage Runway safety.
In addition, Airservices Australia has published a guide for airside drivers, The Airside Drivers Guide to Runway Safety, which focuses on four aspects of operating safely on an aerodrome:
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
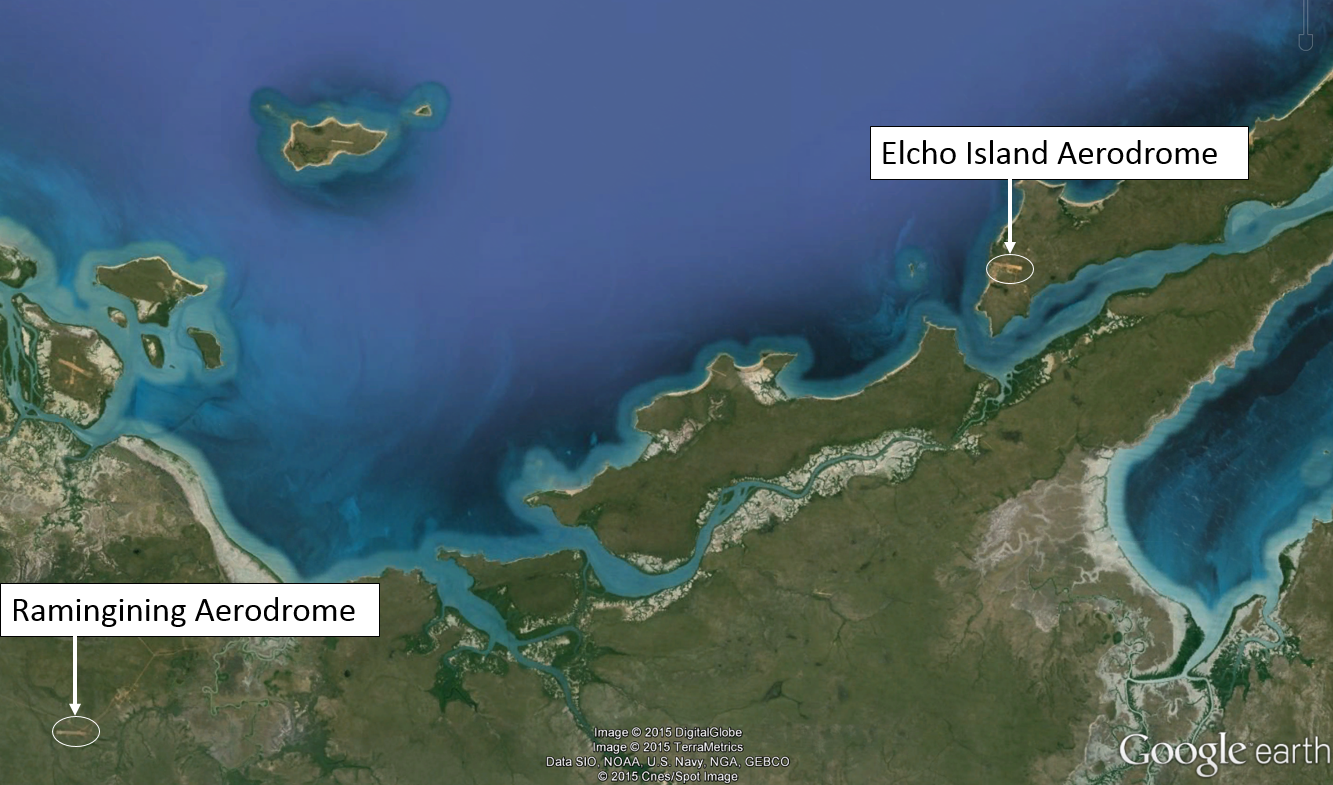
On 14 October 2015, the pilot of a Cessna 172RG aircraft, registered VH-HTP (HTP), conducted a private flight from Ramingining to Elcho Island, Northern Territory, with two passengers on board (Figure 1). The aircraft tracked along the coast from Ramingining, at about 1,500 ft above mean sea level.
Figure 1: Ramingining and Elcho Island, Northern Territory
Source: Google earth – annotated by the ATSB
When about 10 NM from Elcho Island, the pilot broadcast an inbound call on the common traffic advisory frequency (CTAF). The flight crew of an aircraft inbound from Darwin also broadcast on the CTAF, with an estimated arrival time about 3 to 5 minutes earlier than HTP.
At about 1050 Central Standard Time (CST), the pilot of HTP manoeuvred the aircraft to make a straight-in approach to runway 10 at Elcho Island aerodrome. When HTP was passing about 1,300 ft on descent, and 3 NM from the runway threshold, the pilot sighted the other aircraft ahead on the runway.
As the pilot of HTP commenced the pre-landing checks, the flight crew of the landed aircraft broadcast that they were backtracking the full length of the runway. The pilot considered whether it was necessary to make an orbit to allow the aircraft ahead to clear the runway. The pilot elected to continue the approach, closely monitoring the aircraft backtracking on the runway, as well as the aiming point, aircraft profile and position, and airspeed.
As the aircraft ahead taxied clear of the runway, the pilot continued the approach, and selected 10° of flap. However, the pilot omitted to extend the landing gear. The pilot reported the approach was normal, and the conditions were smooth with a light breeze and no turbulence. As the pilot flared the aircraft for landing, the belly of the aircraft contacted the tarmac and the aircraft skidded along the runway. On hearing the scraping sound, the pilot initially applied full power, but the aircraft remained on the ground and came to rest on the gravel beside the runway. The pilot did not hear the stall or landing gear warning horn at any time.
The pilot and passengers were uninjured, and the aircraft sustained substantial damage (Figure 2).
Figure 2: VH-HTP at the accident site
Source: Aircraft operator
Pilot comments
At the point in the pre-landing checks when they would normally extend the landing gear, the pilot assessed they would have to conduct an orbit to give the aircraft ahead time to clear the runway.
The landing gear indication light was located behind the control column and below the pilot’s normal visual field during the approach. The pilot first realised that the landing gear was retracted when the aircraft contacted the runway.
Landing gear warning horn
The Cessna 172RG pilot operating handbook stated that the aircraft was fitted with a landing gear warning system, designed to help prevent the pilot from inadvertently making a wheels-up landing. The system consisted of two switches. One switch would be actuated when the throttle was retarded below 12 inches of manifold pressure. If the landing gear was retracted (or not down and locked), an intermittent tone would sound on the aircraft’s speaker. A second switch in the wing flap system would also sound the horn when the flaps were extended beyond 20° with the landing gear retracted.
Safety message
Initially assessing that an orbit was required led to a break in the pilot’s normal pre-landing checks. The pilot was then distracted monitoring the aircraft on the ground, and the approach. When the pilot assessed that the other aircraft would be clear of the runway and elected to continue the approach, the pilot did not complete the pre-landing checks, and omitted to extend the landing gear.
Generally, distraction is defined as a process, condition or activity that takes a pilot’s attention away from the task of flying. Research conducted by the Australian Transport Safety Bureau identified 325 occurrences between 1997 and 2004, which involved distractions. Of these, 54 occurred during the landing phase of flight.
The Flight Safety Foundation suggests that, after a distraction source has been recognised and identified, the next priority is to re-establish situation awareness by conducting the following:
Identify: What was I doing?
Ask: Where was I distracted?
Decide/act: What decision or action shall I take to get back on track?
The following provide additional information on pilot distraction:
Dangerous Distraction: An examination of accidents and incidents involving pilot distraction in Australia between 1997 and 2004
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 12 October 2015, the pilot completed flight planning, then prepared a PA-31-350 (Piper Chieftain) aircraft, registered VH-HJH, for an aerial survey flight in the southern highlands area of New South Wales. As the flight was to be conducted at 10,000 ft above mean sea level, the pilot also discussed airspace requirements with both Sydney and Canberra Air Traffic Control (ATC) units. Due to potential conflicts with jet traffic at that level, ATC requested the pilot delay the departure from Bankstown, New South Wales, for a few minutes.
Prior to departure, the pilot delivered a safety briefing to the client’s three personnel who would be on board the flight. The pilot reported spending extra time briefing one of the group (Passenger 3) who had not flown in a light aircraft before.
After departure from Bankstown, at about 1300 Daylight Standard Time (EDT), ATC initially provided vectors to the pilot, then cleared the aircraft to the first of many planned waypoints in the area. The pilot reported that both towering cumulus (TC) and cumulus (CU) clouds were beginning to form in the area, and this produced some turbulence, but nothing substantial. However, the pilot remained concerned about Passenger 3, seated at the rear of the aircraft, who appeared to find the conditions difficult to tolerate.
The pilot’s workload remained high. Apart from the pre-planned waypoints, additional ‘landmarks’ were being relayed to the pilot from the client’s operator on the ground. The pilot had to check the landmarks on the chart, translate these requests into usable GPS coordinates, and then enter them into the GPS unit. The pilot then requested an amended clearance from ATC. The pilot visually manoeuvred the aircraft around cloud, and kept the aircraft as ‘smooth’ as possible, so that the survey operators on board could gain the necessary data from their equipment. The pilot also continued to monitor the wellbeing of the passengers, and in particular, passenger 3.
The aircraft was fitted with a main tank (inboard) and an auxiliary tank (outboard), for each of the two engines. As was the pilot’s normal routine, they kept a very detailed fuel log, and continually cross-checked the fuel flow, fuel used, and time remaining in each of the four fuel tanks. The power settings required for the survey were less than normal cruise performance settings.
As the plan was to return to Bankstown at the completion of the survey, the pilot kept a continual awareness of the slowly deteriorating weather there. The pilot reported that the potential alternates of Camden, Goulburn, Canberra and Bathurst remained as options. Thunderstorms were now developing in the Sydney Basin area, although Camden Airport automatic terminal information service (ATIS) still advised of clear conditions at that location. One of the passengers (Passenger 1), seated behind the pilot, discussed the thunderstorms and their impact on the flight with the pilot. As the pilot had kept a detailed fuel log and awareness of the surrounding weather, they were able to reassure the passenger that there was plenty of fuel available to complete the survey and, if necessary, divert to an alternate should a return Bankstown not be possible.
After a little over 2 hours, the clients had almost completed their work, and the pilot prepared to fly to the last waypoint before the return to Bankstown. The weather in the immediate area had now deteriorated even further, and the pilot reported having to divert off track to avoid thunderstorms, although all the alternates remained viable options.
As the pilot was about to make a scheduled fuel tank change from the auxiliary (outboard) tanks to the main tanks, the pilot again checked the fuel log. There was 16 minutes of fuel remaining in the left auxiliary tank (slightly more in the right auxiliary)
The pilot momentarily reflected on the weather versus fuel situation. As the weather between the aircraft’s current location and Bankstown had deteriorated even further, the pilot elected to alter their original plan, and keep the auxiliary tanks selected in order to use another few minutes of the remaining 16 minutes of fuel. This would leave the maximum fuel available in the main tanks. The main tanks in this aircraft are required to be selected during the descent, approach and landing, and, in this case, a possible diversion to an alternate.
During this period, as the pilot diverted around large banks of cloud to keep the aircraft in clear weather and discussed the necessity to fly to the last waypoint with passenger 1, the left auxiliary tank ran dry and the engine surged. This temporary asymmetric situation caused the aircraft to yaw. The pilot reacted immediately and changed the fuel selectors to the main tanks. The engine responded, and power was restored.
The pilot then continued with the remainder of the flight and landed without incident back at Bankstown Airport. At the time of landing, all reserves were intact with ample fuel remaining.
Pilot comments
In hindsight, the pilot reported that the decision to run the last few minutes from the auxiliary tanks may have not been necessary, and probably over-conservative. There had been no operational pressure for them to deviate from the scheduled fuel selection plan. The pilot reported that, due to the combination of distractions, they did not notice the low fuel warning light come on. This may have been further influenced by the amount of light in the cockpit at the time perhaps ‘dimming’ the effect of the red warning light situated on the instrument panel near the compass.
The pilot reported that this was a ‘non-standard’ high workload flight, coupled with deteriorating weather. Although the pilot had over 7,500 flying hours, with about 400 hours on Chieftain aircraft, they found themselves momentarily ‘caught out’. However, due to the aircraft’s altitude at the time, and the pilot’s quick reaction, there was no danger to the aircraft or the occupants.
The pilot also debriefed all passengers when on the ground.
Operator comments
The Chief Pilot advised that the pilot followed all company fuel planning procedures as outlined in the company operations manual. There are no procedures in the manual to advise pilots when they must change tanks to prevent a fuel starvation event. The aircraft landed with 279 litres of fuel, from a total of 690 litres of useable fuel. This equates to 104 minutes, less reserves, using the consumption rate of 160 litres per hour.
The Chief Pilot advised of the importance of regular enroute checks, particularly in a distracting environment.
the aircraft fuel system and kept a detailed fuel log of the four tanks during flight.
However, a high workload, deteriorating weather, and untimely distractions led to a change of a planned procedure and an unplanned outcome of temporary fuel starvation of the left engine.
Another ATSB investigation involving fuel starvation resulted in a more serious outcome, with the aircraft substantially damaged. In that accident, the pilot was also distracted from their scheduled fuel management due to weather; however, the aircraft was at significantly lower altitude. Due to the delayed engine response at low level, the pilot had to conduct a forced landing through fog. The investigation (AO-2015-042) can be found on the ATSB website.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Late in the afternoon of 7 October 2015, a pilot prepared the Robinson 44 helicopter, registered VH-ZWA (ZWA), for a solo training flight. The local flight from Darwin Airport, Northern Territory, was to consolidate the pilot’s knowledge of the local area, and become more familiar with the helicopter, as it was the pilot’s first day in a new job. Earlier in the day, the chief pilot had conducted an acceptance flight with the pilot in ZWA.
The pilot refuelled the helicopter and conducted a pre-flight inspection, before boarding, and completing the pre-start checklist.
The pilot then conducted the following engine start checklist from memory.
Engine start (main actions)
engaged the starter until it fired
engaged the clutch and turned the alternator on
when the clutch light went out, increased the rotor RPM to 79%
conducted a magneto check; and noted that all warning lights were out
began to increase the rotor RPM toward 100% and turned the governor on
Just as the pilot was about to conduct the next checklist item, a low rotor horn check[1], the pilot reported that the helicopter yawed slightly to the left. The pilot quickly checked that the pedals were neutral and put some ‘weight’ on the collective to confirm that it was fully down.
However, the helicopter continued to yaw left rapidly, through about 90° (Figure 1). The pilot applied full right pedal but the helicopter did not respond and continued the yaw, through about 180°, before falling onto its right side. The pilot, who sustained minor injuries, quickly exited the helicopter and the helicopter was substantially damaged (Figure 2).
Pilot experience
The pilot held a Commercial Pilot Licence (H) and a Private Pilot Licence (A). The pilot had logged about 340 hours in helicopters, with about 16 hours of these in the Robinson R44 and about 15 hours in the Robinson R22 helicopter.
Apart from the acceptance flight earlier that day, and a check flight a couple of weeks earlier, the pilot had not flown a R44 for more than three years. The pilot’s most recent helicopter experience was in a MD 520N helicopter. Although the pilot had flown two separate one-hour flights in the last three weeks, the pilot stated they were not current nor experienced on the R44. The pilot reported that flying opportunities had been limited, and spread out over about 4-5 years. During this time, the pilot had also worked as a helicopter support person and as a teacher of commercial helicopter theory subjects.
Figure 1: Skid marks made by VH-ZWA yawing to the left
Source: Operator
Figure 2: VH-ZWA on right side showing damage to main rotor and cabin
Source: Operator
Pilot comments
The pilot arrived from interstate at 0100 on the morning of the accident, ready to start the new job. They signed on for duty at 1000 after 7 hours of sleep. After completing some paperwork, the pilot underwent a one-hour company acceptance flight with the chief pilot. This flight was conducted in ZWA.
After a lunch break, more paperwork was completed before the chief pilot suggested the pilot go for a solo flight, to consolidate their knowledge of the local area and become more comfortable with the R44. The pilot reported feeling a little uncomfortable conducting the solo, but reasoned that it would be a good opportunity to gain some more practice. In addition, the pilot stated being slightly fatigued, and affected by the extra pressure of ‘new employee expectations’.
The pilot made a number of comments regarding different factors of the occurrence, these included:
at the time of the accident, not understanding why the helicopter turned to the left, or yawed so rapidly, particularly after full right pedal had been applied. The pilot later reflected that the pedals must not have been as neutral, as first thought and that this had allowed the yaw leading to the resultant loss of control
suggesting the left yaw may have been from the collective lock being jammed under the collective just enough for the control to feel fully down, but actually have sufficient play to allow the yawing movement.
felt that the helicopter falling onto the right side was consistent with dynamic rollover
Operator comments
The operator acknowledged that the new pilot had low total flying hours and low time on the R44 helicopter. This was combined with only 1.9 hours of flying logged in the last 90 days. Although two recent dual checks had been carried out, the additional solo practice was suggested to allow the pilot some consolidation time. In hindsight, the company realised that the pilot required even more dual time prior to being authorised for any solo practice.
A post-accident engineering inspection did not reveal any mechanical defects with ZWA.
ATSB comment
The ATSB did not conduct an onsite investigation to this accident. The pilot reported not being aware of making any errors during the engine start, but noted that a helicopter is unable to move if the collective is fully down.
In researching several databases for like occurrences, the ATSB found a Robinson 44 accident with similarities, in the United Kingdom. In this accident, the helicopter yawed to the left and fell onto the right side during an engine start. The UK Air Accidents Investigation Branch (AAIB) commented that a rapid yaw to the left could be induced, if too much left pedal is applied at the point of governor engagement, due to the effectiveness of the tail rotor.
The fact that the pilot’s most recent helicopter experience was on a MD 520N, also supports this possibility. The MD520N does not have a traditional tail rotor; it is fitted with a NO Tail Rotor (NOTAR) system, and requires very little pilot input on the pedals. It is probable that the pilot defaulted to this more relaxed pedal pressure during the accident flight.
Other R44 accidents, with relatively inexperienced solo pilots at the controls, were attributed to the pilot’s lack of recency, or inexperience, managing the different handling characteristics of the helicopter, due to the weight shift, which occurred without a person occupying the left seat.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:
Operations manual amendment
All pilots recruited with under 500 hours total time and / or 30 hours in the previous 90 days, must fly with a Grade 1 instructor. This flight is to assess the pilot’s practical and mental status. The Grade 1 instructor is to provide a report on the flight to the Chief Pilot prior to the new pilot undergoing company induction.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of Friday 2 October 2015, track workers were assembling track-side in Laverton, Victoria. They planned to undertake dogspike removal works in preparation for re-sleepering of a section of track on the Altona Loop Line.
At around 0910, the supervisor for the works commenced marking the track to identify those dogspikes to be removed. He was working in a track crossover about 400 m on the Melbourne side of Laverton Railway Station. A lookout had been stationed for his protection.
At about 0916, a Metro Trains Melbourne suburban commuter train arrived at Laverton station, bound for Flinders Street Station in central Melbourne. After its scheduled stop, the train departed Laverton and approached the worksite. The lookout observed the train, warned workers of its approach and signalled to the driver that the track was clear. However, as the train took the crossover, the supervisor was foul of the track, and was struck by the train that was travelling at about 59 km/h. The supervisor suffered serious injuries.
What the ATSB found
The ATSB found that the track was accessed by the workgroup without an assessment of the risks and without the establishment of appropriate risk controls. This meant that not all in the group had a clear understanding of train movements that morning, nor was there a defined position of safety known to all the workers.
It was also concluded that on the train’s approach, the train was given the all clear to proceed prior to the supervisor moving to a position of safety, clear of all tracks.
The supervisor was foul of the track when the train reached his location. It is probable that he expected the train to continue along an adjacent track, and not take the crossover towards his location.
The ATSB also found that there were several other breaches of safeworking procedures that, while not directly contributing to this accident, increased the risks associated with the workgroup’s activities.
What's been done as a result
Since the incident, Metro Trains Melbourne has increased the frequency of audits of infrastructure worker compliance with safeworking procedures.
Safety message
Working in rail corridors carries significant risks that should be mitigated through adherence to established safeworking procedures.
The occurrence
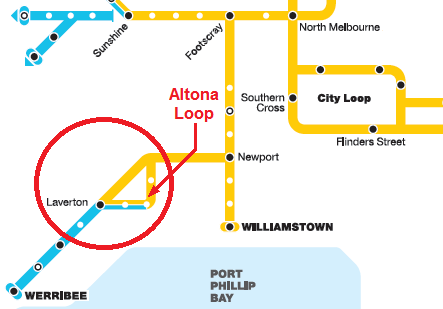
On the morning of Friday 2 October 2015, an infrastructure workgroup was dispatched to Laverton to remove dogspikes from sleepers on the Altona Loop Line (Figure 1). The dogspike removal was in preparation for re-sleepering works scheduled for the following Sunday night. Weather conditions were fine and visibility good.
Figure 1: Altona Loop located between Laverton and Newport
Source: MTM Network Map –adapted by Chief Investigator, Transport Safety (Vic)
The dogspike removal works were to be conducted with trains continuing to run. The Friday had been declared a public holiday, resulting in train services operating to the Saturday timetable.
At about 0830[1] that morning, the Track Force Protection Coordinator[2] (TFPC) for these works arrived at the site. Soon after his arrival, the Rail Safety Worksite Hazard Assessment / Pre-Start form was made available for workers to sign. This form was normally signed after the site safety briefing, but some workers signed it on arrival, prior to the briefing.
At about 0832 the TFPC called Metro Trains Melbourne (MTM) Access Control Centre (Track Access[3]) and advised them of the works to be undertaken on track. The TFPC informed Track Access that he had completed the pre-start hazard assessment and had conducted the rail safety pre-work briefing (safety briefing) to all staff although this, in fact, had not yet been conducted. Track Access then confirmed that the TFPC intended to apply full track protection[4], after which approval to access the track was granted.
While members of the workgroup were assembling, two trains travelled through this section in the Up direction (towards Newport via Altona) and two in the Down direction (via Altona towards Werribee). The last of these trains passed at about 0904.
Soon after, the Infrastructure Works Supervisor (the supervisor) arrived on site. He walked onto the tracks, followed by the TFPC and other track workers. After a short discussion, the supervisor commenced marking the sleepers from which dogspikes were to be removed. The TFPC then returned to an assembly area to commence the safety briefing and on his way back called for lookout protection for the supervisor. A suitably qualified track worker responded to the call and positioned himself at stanchion 724, about 30 m from the supervisor (Figure 2). Other track workers remained in the area between the East Line and Back Platform Line (Figure 2).
Figure 2: Schematic diagram of the accident site and approximate location of track workers
Source: Chief Investigator, Transport Safety (Vic)
The suburban passenger train TD6822 had departed Werribee at about 0905 bound for Flinders Street. At about 0916 the train stopped at Laverton station Platform № 1. The lookout stated that, when he saw the train at the station he alerted the supervisor. He said the supervisor looked at the train, acknowledged the alert and continued marking the sleepers.
At about 0917[5] the train driver sounded the train horn, then departed the station, travelling on the West Line (Figure 2). The lookout heard the horn and reported that he again informed the supervisor that the train was approaching. Two other track workers confirmed they heard the lookout’s warning. The lookout stated that he saw the supervisor move away from the tracks and then he turned to observe the approaching train.
Shortly after departing Laverton station, the train driver noticed track workers between the East and Back Platform Lines. He sounded the horn again and shut-off power, letting the train coast. At that point, the lookout gave the train driver the ‘All-Right’ hand signal. The train had entered the cross-over by this time and the driver sounded the horn again. The lookout continued to observe the train.
The train driver was looking at the lookout as he passed. He then looked ahead and saw a track worker (the supervisor) crouched over and foul of the track. The train driver immediately sounded the horn and then made an emergency brake application. However, the train struck the supervisor. The train speed at that time was 59 km/h.
The supervisor suffered serious injuries. He was treated at the site by paramedics then taken to hospital for further treatment.
There are three broad-gauge and one standard-gauge tracks at this location. The broad-gauge West Line, East Line and Back Platform Line pass through Laverton Railway Station at platforms № 1, № 2 and № 3 respectively (Figure 3). The crossover from the West to the East Line commences about 330 m from the Melbourne-side of Laverton station. The Altona Loop Line is a further 300 m towards Melbourne.
Figure 3: Trackage including station platforms
Source: MTM signalling diagram adapted by Chief Investigator, Transport Safety
Train routing
Weekdays
On weekdays, the Up (to Melbourne) services were routed as follows:
Trains originating from Werribee stopped at Laverton station, platform № 1, then travelled along the West Line direct to Newport bypassing the Altona Loop Line.
Trains originating from Laverton travelled from platform № 3, via the Back Platform Line and Altona Loop Line to Newport.
On weekdays, the Down (from Melbourne) services were routed as follows:
Trains travelling to Werribee would travel direct from Newport to Laverton station platform № 2, via the East Line, bypassing the Altona Loop Line.
Trains terminating at Laverton would travel via the Altona Loop Line and Back Platform line, terminating at platform № 3.
During the morning peak, every third train in each direction was routed via the Altona Loop Line.
On weekends and public holidays:
On weekends and public holidays all services were routed via Altona.
Trains from Werribee to Melbourne stopped at Laverton station platform № 1, then travelled along the West Line, crossing over to the East Line to enter the Altona Loop Line.
Trains from Melbourne to Werribee arrived via the Altona Loop Line and Back Platform Line and stopped at Laverton station platform № 3, then crossed over to the East Line when past the station.
On the morning of Friday 2 October, a public holiday, trains were running to this Saturday schedule. Trains in both directions were running via Altona at 20 minute intervals.
The accident site
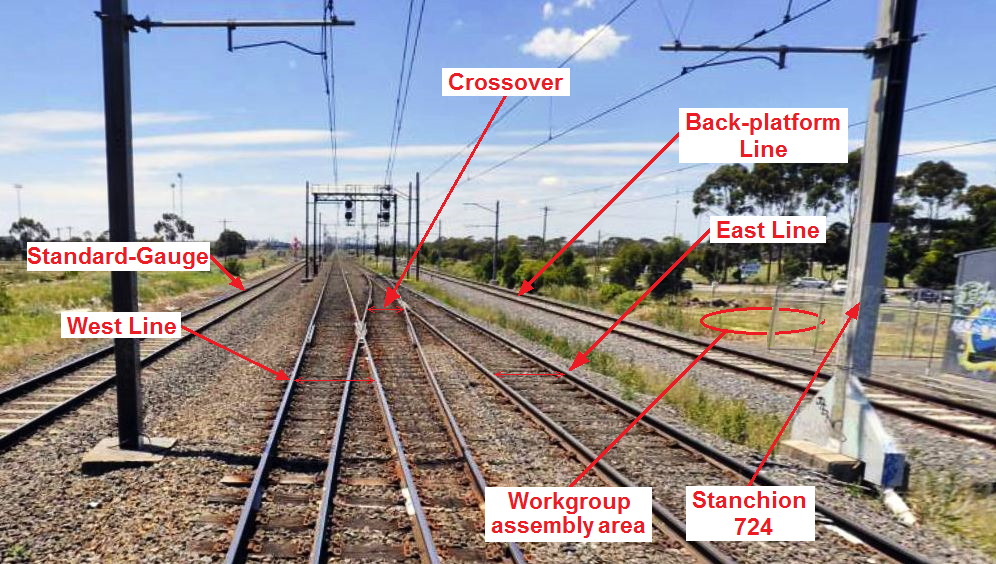
The incident occurred at the crossover from the West Line to the East Line (Figure 4). The supervisor was marking sleepers along the right-hand rail (in the direction of travel) of the crossover towards the East Line. The Lookout was about 30 m away at stanchion 724 between the East Line and the Back Platform Line. The distance between the East Line and the Back Platform Line was about five metres.
Figure 4: The accident site, viewed in the direction of train travel
Source: Public Transport Victoria - PASS Assets - annotated by Chief Investigator Transport Safety
Re-sleepering works
Metro Trains Melbourne (MTM) is the franchise operator of the Melbourne suburban train network. As part of its franchise agreement, MTM is required to maintain track infrastructure and retains infrastructure workgroups at several locations on the network. The workgroups conduct day-to-day maintenance and also undertake project upgrade works.
Re-sleepering(replacing worn sleepers) between Newport and Werribee was scheduled for each night from 4 to 7 October 2015. The section of track along which the incident occurred was scheduled for re-sleepering on the night of 4 October.
Sleeper replacement could be expedited by loosening or removing some dogspikes in advance. These were the works planned for the morning of 2 October. The crew expected to be on-track for about two hours, although there was no set time limit.
Worksite protection
Protection levels
The method or level of protection for a work site is determined by a TFPC after conducting a Site Hazard Assessment. MTM procedures[6] required the TFPC to determine the level of protection commensurate with the risks associated with the job to be undertaken. Track Access would issue an authority for unplanned access where work parties are able to confirm that an on-site rail safety worksite hazard assessment and pre-work briefing had been conducted.
MTM procedures provided for eight levels of protection, Level One[7] being the highest and Level Eight the lowest.
In this instance, Track Access issued an authority based on the TFPC advice that full track protection (Level Six Track Protection) would be applied. This protection involved the posting of inner and outer flagmen and detonators on either side of the work zone.
Safeworking procedures
Consistent with MTM’s Work, Health and Safety systems, only workers with appropriate track-safety qualifications could work on the track. Within its Safety Management System, MTM had developed and implemented safeworking procedures for a range of on-track activities.
Specific requirements were:
Responsibilities of the TFPC
A TFPC was required to be assigned to each workgroup. The role of the TFPC was to keep the rail safety workers and the work site safe from rail traffic. Prior to any work commencing in the rail corridor, the TFPC was required to undertake a rail safety worksite hazard assessment, to determine the appropriate protection requirements for the worksite and to ensure Rail Safety Workers performing worksite protection related tasks were not exposed to hazards. MTM procedures provided that the TFPC would be the only person to speak to the Train Controller, Controlling Signaller and Track Access.
Prior to seeking permission to access the track, the TFPC was to obtain train running information from the Network Controller and/or the Controlling Signaller, then conduct a Rail Safety Pre-Work Briefing. All personnel were to be present at the briefing. The purpose of the safety briefing was to inform workers of the protection to be applied, train running information and the Position of Safety. Once completed, the TFPC could seek approval from Track Access for the workgroup to access the track.
Responsibilities of track workers
Track workers were required to be fit for duty and free of the effects of alcohol and drugs. Prior to accessing the track, workers were required to attend the Rail Safety Pre-Work Briefing. Once this briefing was completed, each track worker was required to sign the safety briefing form as acknowledgement that safety hazards and risk controls were understood.
It also the responsibility of track workers to comply with direction provided by the TFPC and hand signaller / lookout.
Working in the Danger Zone
The Danger Zone was defined as all space within three metres horizontally from the nearest rail and any distance above or below this zone including being on the line, unless a safe place existed or could be created. Work in the Danger Zone was not to commence unless the required worksite protection measures were in place and there was a Position of Safety (POS) identified. A POS is where people or equipment cannot be struck by rail traffic and was required to be outside the Danger Zone or behind a suitable fixed barrier located between the POS and the nearest rail.
When working in the Danger Zone, all personnel were required to move immediately to the designated POS when instructed (by the TFPC, handsignaller or lookout). Once the entire workgroup and the lookout was in a POS, the lookout was to face the approaching train and give an ‘All-Right’ hand signal to the train driver.
All personnel were required to remain in a POS until the TFPC, handsignaller or lookout advised that it was safe to re-enter the Danger Zone.
Lookout Protection
MTM safeworking procedures specified that the TFPC could determine that Lookout Protection was the most appropriate method of protection. Among other things, the TFPC was required to:
determine the number of lookouts
where lookouts should be positioned
advise workers of positions of safety.
In determining the position of the lookout(s), the procedure also specified that the workgroup should be given not less than 25 seconds and not more than 35 seconds notice of approaching traffic, and must be able to move to a POS at least 10 seconds before the arrival of a train.
The procedure specified that the lookout was required to:
stand in a position of safety where they could see approaching rail traffic
be within sight and hearing of the workgroup
maintain effective communication with workers via verbal instruction or by the use of an effective audible warning device. In order to do so, the lookout was to have a red flag (in daylight), a torch with spare batteries (by night) and an effective warning device such as a whistle, air-horn or siren.
Assurance of conformance to safeworking procedures
MTM had developed a system of checks, inspections and audits of workplace conformance to safety and operational procedures. Additionally external agencies, undertook, audits and on-site inspections to verify compliance with the Safety Management System.
External audits scrutinised MTM compliance with the regulatory requirements for transport operators and confirmed that MTM had implemented appropriate measures to address operational and safety matters.
MTM advised that desk-top audits were randomly conducted on Track Access documentation but not on the Rail Safety Worksite Hazard Assessment/Pre-Start documentation.
With regard to on-site inspections, MTM advised that they focussed on major projects at the higher end of track force protection (Level Six and above). There was no record of inspection or audit of the Macaulay or Bell workgroups that were involved in the works at Laverton.
Infrastructure workgroup
The workgroup
As 2 October was a public holiday, the maintenance depots were running at reduced staffing levels and the workgroup was drawn from two depots. The group comprised 13 track workers from the Macaulay and Bell maintenance depots and a contracted backhoe operator.
The workers within the workgroup were appropriately qualified to undertake their roles. They were current with their qualifications and their medicals. Following the incident the workers were tested for drugs and alcohol and all returned negative results.
Infrastructure Works Supervisor
The supervisor was from the Macaulay maintenance depot. He commenced working for MTM in April 2006 and held a Track Force Protection Co-ordinator Level 3.2 certificate[8]. The Supervisor had worked in this section of track many times during the previous eight years. In addition, track force protection through this section was an integral part of the Bridging Course (Level 3.2 & 3.3) and associated examination, which he had completed about two years previously.
His latest medical examination was conducted in November 2011 at which time he was declared fit for duty. The medical certificate was valid for five years. His latest hearing test was in June 2014 and indicated that his hearing ability was within the normal audibility range. The hearing test was valid for two years.
Due to the nature of injuries, the Supervisor was not available for interview.
Track Force Protection Coordinator
The TFPC was also from the Macaulay maintenance depot. He had about 25 years experience as a track worker, and commenced employment with MTM in March 2005. He held a Track Force Protection Co-ordinator Level 3.3 certificate[9].
The TFPC too had worked on this section of track many times in the previous years. He had successfully completed the Bridging Course (Level 3.2 & 3.3) and associated examination about two years previously.
The TFPC’s latest medical examination was in May 2014 at which time he was declared fit for duty conditional on corrective eyesight lenses being worn. The medical certificate was valid for five years. His latest hearing test was in June 2014, the results indicated that his hearing ability was within the normal audibility range. The hearing test was valid for two years.
The TFPC had worked with this supervisor for about 12 months. He was aware no person could access the track without his permission. However, he did not believe he was in a position to challenge the actions of the supervisor.
Lookout
The lookout was from the Bell depot. He had about 20 years experience as a track worker. He commenced working for MTM in September 2005 and at the time of the incident was qualified as a Level 2.2 Hand Signaller[10].
The lookout’s latest medical examination was in January 2013 at which time he was declared fit for duty conditional on corrective eyesight lenses being worn. The medical certificate was valid for five years. His latest hearing test was in June 2014, the results indicated that his hearing ability was within the normal audibility range. The hearing test was valid for two years.
The lookout had not previously worked with the Macaulay workers. When he heard the TFPC calling for a lookout, he volunteered.
The train
TD6822 was a Comeng type, 6-car Electrical Multiple Unit. The train was serviceable and performed within expected parameters. Key events recorded by the train data logger are shown at Figure 5.
Figure 5: Train event recorder key events
Time h:m:s
Event
Distance Travelled(m)
09:16:15
Train arrived at Laverton station (Platform № 1, West Line).
0
09:16:48.6
Train departed Laverton station after sounding the train horn.
0
09:17:10.8
Train horn sounded (when driver observed the track workers).
147
09:17:14.8
Traction off. Train speed 57 km/h.
205
09:17:20.7
The horn sounded again (to acknowledge the ‘All-Right’ hand signal from the lookout). Train speed 58 km/h.
303
09:17:24.2
The horn sounded again (when the driver noticed the supervisor foul of the track). Train speed 59 km/h.
362
09:17:26.9
Emergency brake application. Train speed 59 km/h.
405
09:17:44
Train at stop.
564
The train driver
The driver qualified in November 1989 and since that time has been driving trains on the Melbourne suburban network. He was appropriately qualified, medically fit to operate and returned a negative result when breathalysed for alcohol following the incident.
On arrival at the worksite, the supervisor went onto the track without first confirming with the TFPC that safe access had been arranged. He was followed by other workers. Later, the lookout was posted without receiving a safety briefing.
Prior to going on track, it was necessary to:
Obtain permission from the TFPC and Track Access. The Level Six protection planned for the track works was not yet in place, and so separate protection for this preparatory activity was required. Formalised Lookout Protection (Level Eight) would have been appropriate.
Attend a pre-work briefing that would have included information on train running and discussion on, and designation of, a Position of Safety.
As a result of these activities not being undertaken, the supervisor and the lookout did not receive the benefit of a safety briefing that would have informed them of the outcomes of the worksite hazard assessment, train running, and the designated Position of Safety.
The TFPC attempted to address the risk associated with the supervisor’s uncontrolled access by posting a lookout. The TFPC reported that he believed that he could not challenge the authority and actions of the supervisor, and this may have played some part in him not recalling the supervisor from the tracks to enable formal access processes to be followed.
Authority for passage of train
The lookout reported that after calling out to warn of the approaching train, he saw the supervisor move away from the track, whereupon he (the lookout) turned to face the train in response to hearing its horn.
However, the supervisor was on the track when the train arrived. It is probable that the lookout saw the supervisor begin to react, and in his mind, decided that the supervisor was moving off track. In the belief that the track was or would be clear, he gave the driver the ‘All-Right’ hand signal.
Supervisor not clear of the track
Upon the approach of train TD6822, it is unlikely that the supervisor would have remained on-track had he been aware that the train would cross over to the East Line. It is probable that he believed that the train would continue along the West Line, and that he was in a safe position at his location near the East Line.
As the train approached, it is possible that the supervisor did not consider that trains were running to the Saturday timetable, and via the East Line and the Altona Loop Line. That the train stopped at platform № 1 at Laverton station may have reinforced an expectation that the train would continue direct to Newport along the West Line, as it would have done on a normal weekday.
Safeworking Protocols
In addition to the initial uncontrolled access to the track that is considered a contributory safety factor, there were several other actions of the workgroup that were contrary to established safety procedures. While probably not directly contributory to the incident, the actions increased the risks associated with the workgroup’s activities.
The additional actions that were deviations from MTM’s safeworking processes included:
The TFPC advised MTM’s Track Access office that a safety briefing had been conducted when this was not the case.
Members of the workgroup were aware that the Rail Safety Pre-Work Briefing form was to be signed only after the safety briefing had been completed, yet several signed the form in advance.
The TFPC instructed the lookout to access the track without a safety briefing.
The lookout took up his position without a red flag and an effective warning device.
When the lookout warned of the approaching train, the track workers did not move to a Position of Safety that was clear of all tracks.
Findings
From the evidence available, the following findings are made with respect to the track worker being struck by a passenger train near Laverton station, Victoria on 2 October 2015. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
The track was accessed by the work crew without an assessment of the risks and without the establishment of appropriate risk controls.
An ‘All-Right’ hand signal was given to the train driver before the supervisor had moved to a Position of Safety clear of all tracks.
The supervisor did not move to a position of safety as the train approached. He probably expected the train to proceed directly along the West Line and not take the crossover to his location.
Other factors that increased risk
The actions of the workgroup contravened several safeworking protocols, increasing the risks associated with their activities.
Safety actions
Additional safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety actions in response to this occurrence.
Additional safety action taken by Metro Trains Melbourne
Metro Trains Melbourne advised that since this occurrence:
Field audits of safeworking practices have been increased.
There has been an improved system of record keeping and review of those audits.
The increased field inspections are being used as an opportunity to educate and refresh track workers on safeworking procedures.
Sources and submissions
Sources of information
The sources of information during the investigation included:
Metro Trains Melbourne
Data logger from train TD6822
The workgroup
The train driver.
References
MTM document L1-OPS-PRO-018 Planning Work Site Protection In The Rail Corridor
MTM document L0-SQE-PRO-037 Lookout Protection
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Metro Trains Melbourne, the supervisor, the TFPC, the lookout, the train driver, the Office of the National Rail Safety Regulator and Transport Safety Victoria
Submissions were received from the Office of the National Rail Safety Regulator (ONRSR) and Metro Trains Melbourne (MTM). The submissions from those parties were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 1 July 2015, a Cessna C650, registration N692BE, was involved in a serious incident during take-off from Corlu Airport Turkey.
The Aircraft Accident Investigation Board of Turkey (KAIK) commenced an investigation into the circumstances of the accident. As part of its investigation, KAIK requested assistance from the Australian Transport Safety Bureau (ATSB). To protect any information supplied by KAIK to the ATSB, and the ATSB's investigative work to assist KAIK, the ATSB initiated an investigation under the Transport Safety Investigation Act 2003.
The ATSB was recently advised by the KAIK that they had ceased their investigation. Consequently, the ATSB has concluded its activities in support of the KAIK investigation. Enquiries relating to the investigation into this occurrence should be directed to KAIK.
On 10 July 2015, the pilot of a Piper PA-28 aircraft, registered VH-MHI (MHI), conducted a flight from Porepunkah to Lilydale, Victoria (Figure 1). In Lilydale, the pilot refuelled the aircraft, filling the tanks to full (189 L). Then the aircraft departed for Parafield, South Australia at about 1400 Eastern Standard Time (EST), with the pilot and two passengers on board.
Figure 1: Approximate aircraft track from Porepunkah to Lilydale and Adelaide
Source: Google earth annotated by the ATSB
As the aircraft passed overhead Nhill, Victoria, the pilot assessed the fuel status. The fuel gauges indicated about 100 L of fuel remaining, which the pilot reported was in agreement with the expected fuel consumption rate. The pilot calculated that based on 90 minutes flight time remaining, 60 L of fuel was required, plus 30 L fixed reserve. Therefore, the pilot assessed that sufficient fuel remained to complete the planned flight, and elected to continue towards Parafield.
The pilot reported that the forecast cloud base was 4,500 ft in the area around Tailem Bend, South Australia. However, when approaching Tailem Bend at 4,500 ft above mean sea level (AMSL), the pilot was required to deviate and descend around cloud to remain in visual meteorological conditions (VMC). This deviation increased the track miles flown.
At about 1750 Central Standard Time (CST), the pilot contacted Adelaide Centre air traffic control (ATC), and advised that they were overhead Tailem Bend, and requested a clearance into the Adelaide control zone. The controller assigned the pilot a unique transponder code, and the aircraft tracked towards Murray Bridge, South Australia. At about 1755, when abeam Murray Bridge, the pilot advised ATC of the aircraft’s current position. The controller confirmed the pilot had the correct transponder code and advised that the aircraft was not visible on the ATC radar display and they were therefore to remain outside Class C airspace. About 2 minutes later, the pilot recycled the transponder, then advised ATC of the code they had selected on the transponder. The controller responded that the aircraft was still not visible on the radar display. In addition, they advised the pilot that if they were unable to identify the aircraft on radar, the pilot would not be given a clearance to enter Class C airspace. The pilot repeated the transmission about 3 minutes later, when about 30 NM south-east of Adelaide at 4,500 ft. Again, the controller advised that the aircraft was still not visible on the radar display, and would therefore not be able to obtain a clearance into controlled airspace.
The pilot then switched the transponder off for about one minute, before switching it back on. At about 1803, the Adelaide Centre controller told the pilot that the Tower controller at Parafield Airport had advised that they were unable to see Mt Lofty from Parafield due to cloud. The pilot advised the controller that the aircraft was then approaching Strathalbyn and the weather appeared to be clear towards Adelaide (Figure 2). The controller then stated that the aircraft was now visible on the radar display.
Figure 2: Approximate aircraft track from Strathalbyn to Adelaide
Source: Airservices Australia annotated by the ATSB
At about 1805, the pilot again reported to ATC that they were approaching Strathalbyn at 4,500 ft and the controller advised the pilot to standby for a clearance. About 1 minute later, the controller identified the aircraft on the radar display, about 30 NM south-east of Adelaide and cleared the pilot to track to Port Noarlunga, then expect to track up the coast to Port Adelaide and on to Parafield.
At about 1812, the pilot was becoming increasingly concerned about the aircraft’s fuel status, with both fuel gauges indicating close to empty. Therefore, the pilot requested a clearance to track overhead Adelaide to shorten the distance remaining to Parafield. About 2 minutes later, the controller cleared the aircraft to track direct overhead Adelaide city then to Port Adelaide.
When about 15 NM southeast of Adelaide, the engine ran roughly. The pilot changed the selected fuel tank from the left to the right, and assessed that the left tank was empty. The left fuel gauge was indicating empty and the right gauge was indicating just above empty.
At about 1816, the pilot declared a PAN[1] due to low fuel and requested a clearance to track direct to Adelaide Airport for a landing there. The controller advised the pilot to expect a clearance to land on runway 30 at Adelaide. About 5 minutes later, the pilot was cleared to conduct a visual approach to runway 30 and the controller suggested to the pilot to ‘remain as high as you can for as long as you can’.
At about 1824, the pilot contacted the Adelaide Tower controller and switched on the aircraft landing lights. Two minutes later, the tower controller cleared MHI to land, and the aircraft subsequently landed at Adelaide on runway 30.
After the flight, the pilot dipped the fuel tanks. The dipstick indicated no fuel in either tank. The calibration for the dipstick in that aircraft stated that zero fuel would indicate on the stick when 20 L or less remained in either tank. As the left tank had run dry, the pilot assessed there had been less than 20 L of fuel remaining after shutting down the aircraft.
Weather
The weather forecast for Parafield aerodrome (TAF) valid from 1730 CST included wind from 320° at 15 kt, showers of light rain, and broken[2] cloud at 4,500 ft above ground level (AGL). The weather forecast for Adelaide aerodrome (TAF) included wind from 320° at 15 kt, showers of light rain, and broken cloud at 4,500 ft AGL.
The area forecast for Area 50 valid for the flight included wind at 5,000 ft AMSL from 280° at 30 kt, and broken cloud with base from 3,000-8,000 ft AMSL and scattered showers of rain.
Pilot comments
The aircraft was filled with fuel and close to maximum weight when departing Lilydale. The aircraft departed about 90 minutes later than planned from Porepunkah for Lilydale and was then further delayed waiting for fuel in Lilydale. Prior to those delays, the pilot had anticipated arriving in Parafield before last light. The pilot had planned to refuel (during daylight hours) at Murray Bridge if it was assessed as necessary during the flight. However, there was no aerodrome lighting available at Murray Bridge. There were also numerous airfields between Nhill and Parafield suitable for landing during daylight hours, if additional fuel was required. After dark, Nhill was the last airport with pilot activated lighting (PAL) before Adelaide, but fuel was only available at Nhill by prior arrangement.
The pilot had planned to conduct the cruise at 4,500 ft, but had to descend close to the lowest safe altitude of 3,800 ft to stay clear of cloud. The delay with radar identification meant they had to divert from the direct track to remain outside controlled airspace. These factors contributed to the low fuel state.
Airservices Australia comments
Airservices Australia provided the following comments:
If the aircraft’s transponder had been operating normally, the controller should have been able to identify the aircraft at the altitude and location where the pilot first contacted Adelaide Centre.
At the pilot’s planned altitude of 4,500 ft, the aircraft was not required to divert to remain outside controlled airspace until within 20 NM of Adelaide Airport.
The controller would have facilitated a clearance without radar identification, if the pilot had declared a PAN when initially requesting a clearance.
Fuel endurance
The following table provides a summary of the pilot’s fuel planning figures.
Table 1: Fuel calculation
Fuel
Pilot plan
Taxi and climb allowance
10 L
Planned fuel required
4 hours x 40 L = 160 L
Reserve fuel
30 L
Total fuel required
200 L
The pilot operating handbook (POH) for the Piper PA-28-181, Cherokee Archer II, stated that the fuel capacity was 189 L, with 182 L usable fuel. The handbook provided graphs to estimate fuel range, dependent on pressure altitude, power setting from 55% to 75%, and with mixture leaned to 100 °F rich of peak exhaust gas temperature (EGT) for ‘best power mixture range’, and with mixture leaned to peak EGT for ‘best economy range’. The pilot reported an airspeed of about 120 kt, indicating power setting between 75% power and full throttle at 4,500 ft AMSL, based on the ‘Speed power – performance cruise’ graph in the POH. At 75% power at 4,500 ft the graph indicated a range of about 500 NM with 45 minutes reserve fuel, in zero wind conditions.
The pilot planned on fuel consumption of 40 L/hr and reported that the aircraft usually consumed about 37 L/hr when cruising above 5,000 ft. The pilot had set the fuel mixture control slightly rich of peak EGT. The planned total distance was about 400 NM and total time about 4 hours. The pilot reported that the airspeed was indicating 120-150 kt.
Lilydale to Parafield is about 370 NM in a straight line, and it is about 173 NM from Nhill to Parafield. The direct track from Lilydale to Parafield is 296°. Based on the forecast wind for the area at 5,000 ft, the aircraft would have encountered a headwind of about 25-30 kt. The pilot estimated that the aircraft had a headwind of about 10 kt.
After passing Nhill, the pilot selected the cabin heat on and thought this may have increased the fuel consumption. According to the aircraft’s POH, the cabin heat is routed from air from around the manifold exhaust and does not increase fuel consumption. They did not have carburettor heat on at any stage of the flight.
Safety message
The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. One of the safety concerns relates to aircraft fuel management.
Pilots are reminded of the importance of careful attention to aircraft fuel state. ATSB Research report AR-2011-112 Avoidable accidents No. 5 Starved and exhausted: Fuel management aviation accidents, discusses issues surrounding fuel management and provides some insight into fuel related aviation accidents. The report includes the following comment:
Incidences of fuel exhaustion often happen close to a flight’s destination and, if it occurs when the aircraft is close to landing, it may offer the pilot less time and opportunity to successfully manage the situation.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.