Loss of cyclic control and in-flight break-up involving Robinson R22, VH-HGU, 7 km north-north-west of Cloncurry Airport, Queensland, on 2 August 2017

Final report

Report release date: 21/07/2020

Safety summary

What happened

On the morning of 2 August 2017, the pilot of a Robinson R22 Beta II helicopter, registered VH‑HGU and operated by Cloncurry Mustering Company, departed Cloncurry Airport, Queensland, on a ferry flight in preparation for an aerial mustering operation. About 3 minutes after take-off, the pilot experienced a loss of control and the helicopter broke-up in-flight. The helicopter collided with terrain about 7 km north-north-west of Cloncurry. The pilot, who was the only occupant, was fatally injured and the helicopter was destroyed.

What the ATSB found

The ATSB found that the helicopter had recently undergone a 2,200-hour overhaul and this was the first commercial flight since that time.

The on-site examination established that the bellcrank in the helicopter cyclic control assembly was missing a fastener, which allowed the assembly to disconnect in-flight. The ATSB concluded that it was likely that the fastener’s self-locking nut was either not reinstalled or it was inadequately torqued during the overhaul. While it could not be determined what had occurred to result in this condition, it was noted that Cloncurry Air Maintenance (CAM) did not use the work-pack to record and track all maintenance activities during the overhaul, which extended over a period of almost 4 months.

The ATSB noted that, in the years leading up to the accident, the CAM workforce structure had changed in a manner that reduced the levels of its qualifications and experience. In the month leading up to the accident, the CAM workforce was operating at a very high workload, which likely exceeded their workforce capability and reduced the chief engineer's capacity to oversight maintenance activities.

Cloncurry Air Maintenance (CAM) had limited internal independent oversight of maintenance activities to evaluate its quality performance. The organisation was subject to both contracted and regulator audit activities in the years leading up to the accident. The ATSB reviewed two of the work-packs sampled during the audits and noted that discrepancies in their maintenance documentation practices were visible to the auditors. However, the auditors had not identified any issues associated with those practices, and therefore, the audits were of limited benefit to CAM.

It was also established that CAM were re-using the MS21042L-series nuts on critical fasteners without replacing them with D210-series corrosion resistant nuts in accordance with the manufacturer's instructions. However, the ATSB also found that the re-use of self-locking nuts was a common and accepted industry practice.

What's been done as a result

Cloncurry Air Maintenance have improved their maintenance practices, which has included progressive certification for tasks, adopting the helicopter manufacturer’s checklists for their inspections, removing all untracked MS-series self-locking nuts from stores, and completing inspections of the flight controls on all the Cloncurry Mustering Company helicopters with nil defects reported.

In March 2019, the Australian Transport Safety Bureau issued a safety advisory notice advising all Australian maintenance personnel for Robinson helicopters to ensure that before re-using a self‑locking nut, that the correct part number is fitted, and that the D210-series corrosion-resistant nuts are used for reassembly of critical fasteners in accordance with the Robinson Helicopter Company instructions for continued airworthiness.

As a result of this accident and other investigations by the Civil Aviation Safety Authority, the regulator issued airworthiness bulletin 67-005: Robinson Helicopter Flight Controls – Independent Inspections. The bulletin highlighted the need for independent inspections to be conducted and ‘recorded consecutively with each adjustment made during rotor tracking and balancing’ activities. In addition to several recommendations, the bulletin identified several human factor elements that could impact maintenance inspection performance, and highlighted the need for extra caution to be exercised during post-maintenance flights as per the guidance provided by Robinson.

Safety message

Although verbal communications are an important method of explaining and understanding problems, they are not a reliable means for capturing essential tasks over an extended time‑period. This accident highlights the importance for maintenance organisations to consider the human factors elements associated with their practices, capture them in their documented quality control procedures, and ensure they are complied with.

Audits are essential for independently verifying the effectiveness of an organisation's processes and procedures. This accident reinforces the importance of auditors inspecting the evidence collected during an audit to ascertain whether or not the requirements are being met, specifically conformance with the relevant standards. Audits may also be used to identify potential underlying human factors issues, which may be raised as an opportunity for improvement to inform the auditee of best industry practices.


The occurrence

On the morning of 2 August 2017, the pilot of a Robinson R22 Beta II helicopter, registered VH‑HGU and operated by the Cloncurry Mustering Company (CMC), was conducting a ferry flight from Cloncurry Airport, Queensland in preparation for an aerial mustering operation at a station to the north of Cloncurry.

The helicopter had departed from Cloncurry Airport just after first light, at about 0659 Eastern Standard Time.[1] The pilot’s colleagues reported observing the pilot warming up the engine and then take-off with a normal profile to the north. They also stated that the helicopter sounded normal on departure.

Shortly after the helicopter departed, staff from CMC and their maintenance organisation, Cloncurry Air Maintenance (CAM), observed a plume of smoke to the north. A company pilot noted that the smoke was in the general direction of VH-HGU’s track and was drifting towards the west. The pilot attempted to contact the accident pilot via mobile phone at 0713, but the call went to message bank. The company pilot departed with a colleague in another R22 towards the smoke.

The helicopter wreckage was located about 7 km north-north-west of Cloncurry Airport at about 0718 (Figure 1). The pilot was fatally injured and the on board global positioning system device indicated the accident occurred at about 0702.

Figure 1: VH-HGU accident site

Figure 1: VH-HGU accident site.
Source: ATSB

Source: ATSB

On landing near the wreckage, the company pilot made a phone call to report the accident, and activated an emergency beacon to assist the emergency services with locating the site. The pilot noted there was very little soil disturbance, normally associated with main rotor blade strikes to the ground during an accident sequence. The pilot also considered the location of the accident site was consistent with the track the accident pilot would have flown to the station for the contracted work. Soon after, the emergency services arrived at the accident site and took control of the scene. The accident was not considered survivable.

Another company pilot, who departed Cloncurry just prior to the accident pilot, reported hearing no communications on the company’s mustering radio frequency. At 0702:29, an unidentified transmission occurred on the Cloncurry Airport common traffic advisory frequency. However, it was only momentary (about 1 second duration) and did not contain any voice data.

Powerline inspection

The most significant feature near the accident site was the Ernest Henry Mine high voltage powerlines, about 70 m to the west of the accident site. The first responders from CMC noted the powerlines were intact and that no other aircraft were known to be in the area at the time. Staff from the powerline company attended the site with a remotely piloted aircraft to inspect the pylons and lines. On completion of that inspection, they concluded there was no evidence of impact damage.

__________

  1. Eastern Standard Time (EST): Coordinated Universal Time (UTC) +10 hours.

Context

Pilot information

The pilot started flying training in 2002, and had been employed by the Cloncurry Mustering Company (CMC) since 2004, and held a Commercial Pilot Licence (Helicopter) with a flight instructor rating for low‑level helicopter operations and aerial-mustering. The pilot’s most recent flight review was on 15 November 2016 in an R22 helicopter. The pilot held a Class 1 Aviation Medical Certificate with no restrictions and an expiry date of 2 February 2018. On 6 January 2017, 10,000 flying hours experience was recorded on the pilot’s medical examination questionnaire.

On 1 August 2017, the night before the accident flight, the pilot went to bed at about 2000. The next morning, the pilot left home for work at about 0530. Several colleagues spoke with the pilot between 0600 and 0700 at the company’s hangar facility at Cloncurry Airport and reported the pilot’s demeanour as normal.

From the operator’s records, the accident occurred on the pilot’s third consecutive day of flying, which included 12.2 hours flying in the previous 2 days. Prior to that period, the pilot had not flown for 8 days. The time of the accident was not in the circadian low period and did not include an extended period of duty.

Helicopter information

General information

VH-HGU was a two-seat Robinson Helicopter Company (RHC) R22 Beta II helicopter, serial number 4335, powered by a 4-cylinder, carburettor Textron Lycoming O-360-J2A engine (Figure 2). It was manufactured in 2008 and registered in Australia in July of the same year. The helicopter was added to the CMC fleet on 16 February 2017.

Figure 2: Example R22 helicopter

Figure 2: Example R22 helicopter.
Source: Queensland Police Service

Source: Queensland Police Service

Drive system

Engine power is transmitted to a V-belt sheave bolted to the engine output. The V-belts transmit power to the upper sheave, which transmits power forward to the main rotor and aft to the tail rotor. Flexible couplings[2] are located at the main gearbox input (forward flexible coupling) and at each end of the tail rotor drive shaft (intermediate and aft flexible couplings).

Rotor systems

The main rotor has two blades mounted to the main rotor hub by coning hinges.[3] The hub is mounted to the main rotor shaft by a teeter hinge. Droop stops for the main rotor blades, mounted near the top of the main rotor mast, provide a teeter hinge friction restraint, which normally prevents the rotor from teetering (rocking) while stopping or starting. Elastomeric teeter stops,[4] mounted in brackets in-line with the main rotor blades, limit the teetering during normal flight conditions and will provide a damage witness mark if there is excessive teetering of the main rotor system in-flight. The main and tail rotor systems are fitted with pitch links to transmit the flight control inputs to the rotor blades.

Flight controls

Primary controls are actuated through push-pull tubes and bellcranks. Flight control operation is conventional. The tail rotor pedals change the pitch of the tail rotor blades, and therefore the thrust, of the tail rotor system, which provides directional control. The collective[5] lever controls the amount of thrust (lift) produced by the main rotor disc. Raising or lowering the collective lever will raise or lower the swashplate,[6] which will alter the pitch on both main rotor blades to increase or decrease the main rotor thrust. The collective lever also incorporates a twist grip to provide the pilot with full manual control of the engine throttle.

The cyclic[7] control tilts the main rotor disc to point the rotor thrust in the desired direction of flight. Fore-aft movement of the cyclic provides the longitudinal (pitch) control of the main rotor disc. Forward movement will tilt it down at the front and up at the back, and aft movement will tilt it up at the front and down at the back. There is a single push-pull tube connection to the swashplate at the rear of the main rotor mast to provide the pitch control. Left-right movement of the cyclic provides lateral (roll) control of the main rotor disc. There are two push-pull tubes connected to the swashplate, either side of the main rotor mast, to tilt the disc left or right.

Recent maintenance history

The helicopter had accumulated about 4,365 hour’s total time-in-service at the time of the accident. When CMC acquired VH-HGU, in February 2017, it had about 80 hours remaining before it was due for its second 2,200-hour overhaul. Therefore, the operator’s maintenance organisation, Cloncurry Air Maintenance (CAM), completed a 100-hour inspection at the time of the acquisition and the helicopter was operated by CMC until the 2,200-hour overhaul was started on 12 April 2017.

The 2,200-hour overhaul involved the disassembly, inspections, reassembly and checks of the helicopter. All flight control push-pull tubes were sent for non-destructive testing and found serviceable. The helicopter was reassembled and a weight and balance, and fuel calibration was completed. The flight controls were rigged and then the helicopter was subject to a 100-hour inspection before a ground run, track and balance[8] of the main rotors, and autorotation RPM check were completed on 28 July 2017.

On 31 July 2017, a 15-minute local area flight was conducted to confirm the serviceability of the helicopter. Following that flight, CAM staff certified for all the tasks in the 2,200-hour overhaul work-pack, including independent inspections[9] of the engine and flight controls, and issued the maintenance release.[10]

The next time the helicopter was operated was the accident flight.

Loading and performance

The ATSB’s calculations indicated the helicopter was within the prescribed weight and balance limits for the flight. Using the local environmental conditions, the out-of-ground‑effect[11] hover performance weight was within limits at the helicopter’s certified maximum all-up-weight of 622 kg.

Meteorological information

The weather conditions recorded at Cloncurry Airport at 0700 included a wind speed of 1 kt from 100°, a temperature and dewpoint[12] of 14 °C and 5 °C respectively, and a QNH[13] of 1015 hPa. The Cloncurry aerodrome forecast[14] for the period from 0400 to 1600 included a wind speed of 6 kt from 170° and CAVOK[15] conditions. Given the insignificant conditions, the ATSB determined that it was very unlikely that the weather contributed to the circumstances of the accident.

Global positioning system data

The pilot’s Garmin GPSMAP196 navigation device was recovered from the wreckage for examination and analysis by the ATSB. The global positioning system (GPS) had several track logs, which included the accident flight and a previous mustering flight.[16]

Figure 3 depicts the helicopter’s GPS track from take-off to the accident site, and Figure 4 depicts the position of the main wreckage relative to the last reliable GPS data point and vicinity to the powerlines. Table 1 provides the data points for the accident flight. The ATSB considered the final data point (14), which was beyond the accident site, to be an unreliable point for the purpose of analysis as it very likely represented a predictive point.[17]

Figure 3: Accident flight GPS track

Figure 3: Accident flight GPS track.
Source: Google Earth, annotate by the ATSB

Source: Google Earth, annotate by the ATSB

Figure 4: Accident site datum relative to the last reliable GPS data point
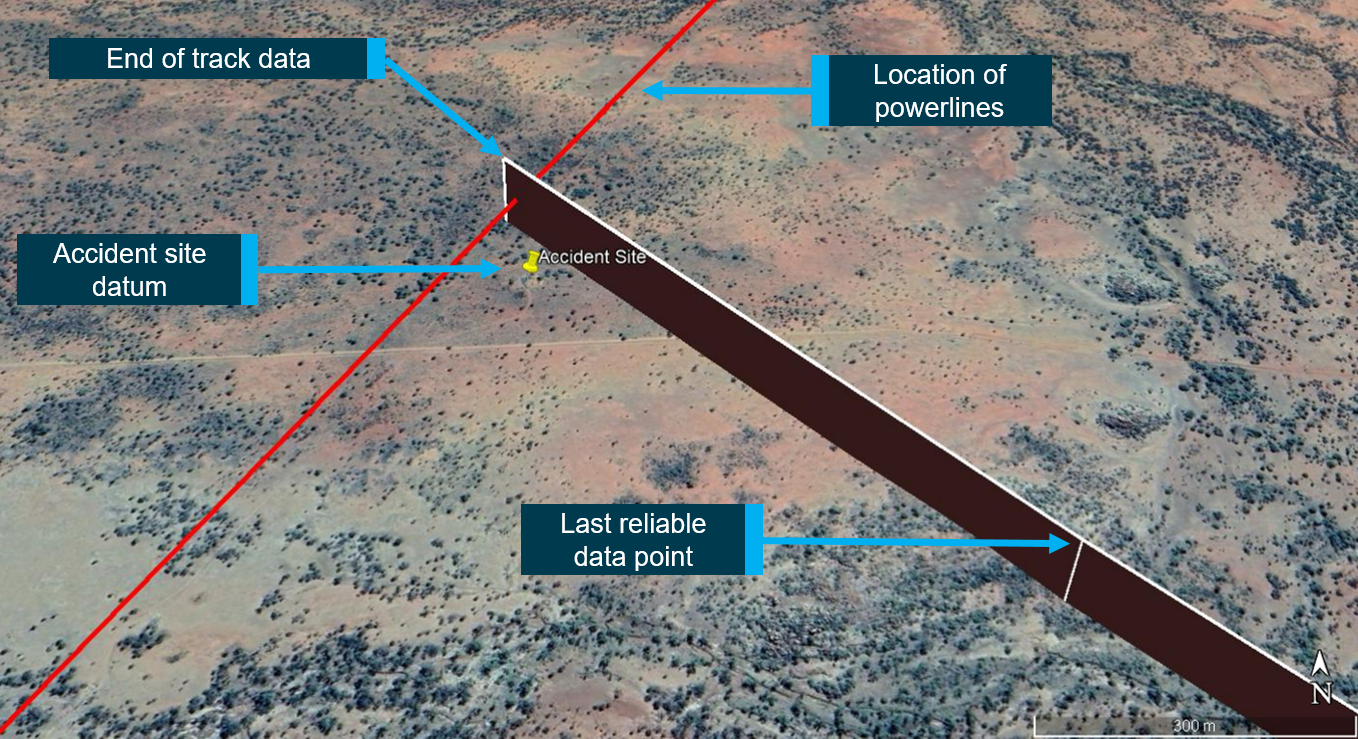
Figure 4: Accident site datum relative to the last reliable GPS data point.
Source: Google Earth, annotate by the ATSB

Source: Google Earth, annotated by the ATSB

From Table 1, the changes in altitude and vertical speed were all positive from the departure point to the last reliable data point (13). In addition, the average ground speeds between the data points were relatively stable leading up to point 13. This suggested the helicopter had a reasonably steady climb flight profile. At point 13, the helicopter was about 279 ft above the local terrain, and about 82-148 ft above the height of the Ernest Henry powerline towers.[18]

Table 1: Accident flight data points

Data pointTimeTime interval (s)GPS altitude (ft)[19]Interval average vertical speed (ft/min)Interval average ground speed (kt)
1.0658:51-628--
2.0659:122164549.720
3.0659:21965563.445
4.0659:331266970.565
5.0659:431067537.471
6.0659:571469374.578
7.0700:182171562.881
8.0700:3517756144.781
9.0700:481377380.383
10.0701:061880295.183
11.0701:241883094.182
12.0701:452186086.284
13.0701:5914901175.889
14.0702:2728964131.566

Medical and pathological information

Pilot’s medical history

The pilot was a patient of the Cloncurry Flinders Medical Centre since 2005, which included flight crew medical examinations by the local designated aviation medical examiner (DAME). In 2011, after a diagnosis of mild hypertension, the pilot started a prescribed daily dose of 150 mg Irbesartan.[20]

Post-mortem and toxicology results

The post-mortem examination established that the pilot received extensive injuries associated with a rapid deceleration and the cause of fatality was ruled as multiple injuries as a result of the accident. The examination also found 75 per cent eccentric stenosis[21] in the mid segment of the left anterior descending artery of the pilot’s heart. This was characterised as severe atherosclerosis.[22] The forensic pathologist reported:

It is theoretically possible that this may have precipitated abnormal heart rhythm leading to pilot incapacitation and subsequent accident. This scenario can be neither confirmed nor excluded on the basis of autopsy examination.

A low concentration of alcohol was detected in the blood, which was considered to be ‘likely post‑mortem contamination, probably due to decomposition’. No drugs, including Irbesartan, were detected.[23]

Specialist advice

In consideration of the forensic pathologist’s scenario, the ATSB conducted a follow-up on the pilot’s health with the Cloncurry DAME, the CASA Principal Medical Officer (PMO) and the Director of the Clinical Forensic Medicine Unit for the Queensland Department of Health.

The PMO noted the other arteries and heart were found with no discernible abnormality, therefore, the conditions had not dispersed through the cardiovascular system. The PMO also reported that it could not be determined with certainty if the pilot experienced abnormal heart rhythm unless the heart was being actively monitored. Queensland Health reported that the ‘consequences of high blood pressure as a clinical issue were not noted in the autopsy report. In particular, there was no evidence of a stroke and no indication of a heart attack’.

The Cloncurry DAME reported the dosage of Irbesartan was moderate and that it ‘would have been unlikely to cause any symptoms of hypotension causing dizziness or disorientation’. Queensland Health and the PMO reported that missing a single dose of Irbesartan would not be likely to cause any issues clinically.

Wreckage and impact information

The wreckage examination included an initial on-site inspection, followed by a review of the accident site images. The photographic review resulted in a second accident site visit to excavate the wreckage and retrieve a component of interest, which was the bellcrank from the cyclic control assembly.

Initial on-site examination

The helicopter wreckage was located amongst termite mounds, in a sparsely treed area. The main wreckage had been subject to a significant post-impact fire, which had reduced the cabin area to ash, molten aluminium, and fibreglass mat. The airframe was oriented south-east on a heading of about 140°, which was in the opposite direction to the helicopter’s recorded flight path. Small pieces of debris were scattered around the wreckage in a radius of about 20 m in most directions. The windscreen perspex was unburnt, shattered into small pieces and contained in an area of about 2 m2 just forward of the cabin area. All the major components were identified within the debris field (Figure 5).

Figure 5: Main wreckage
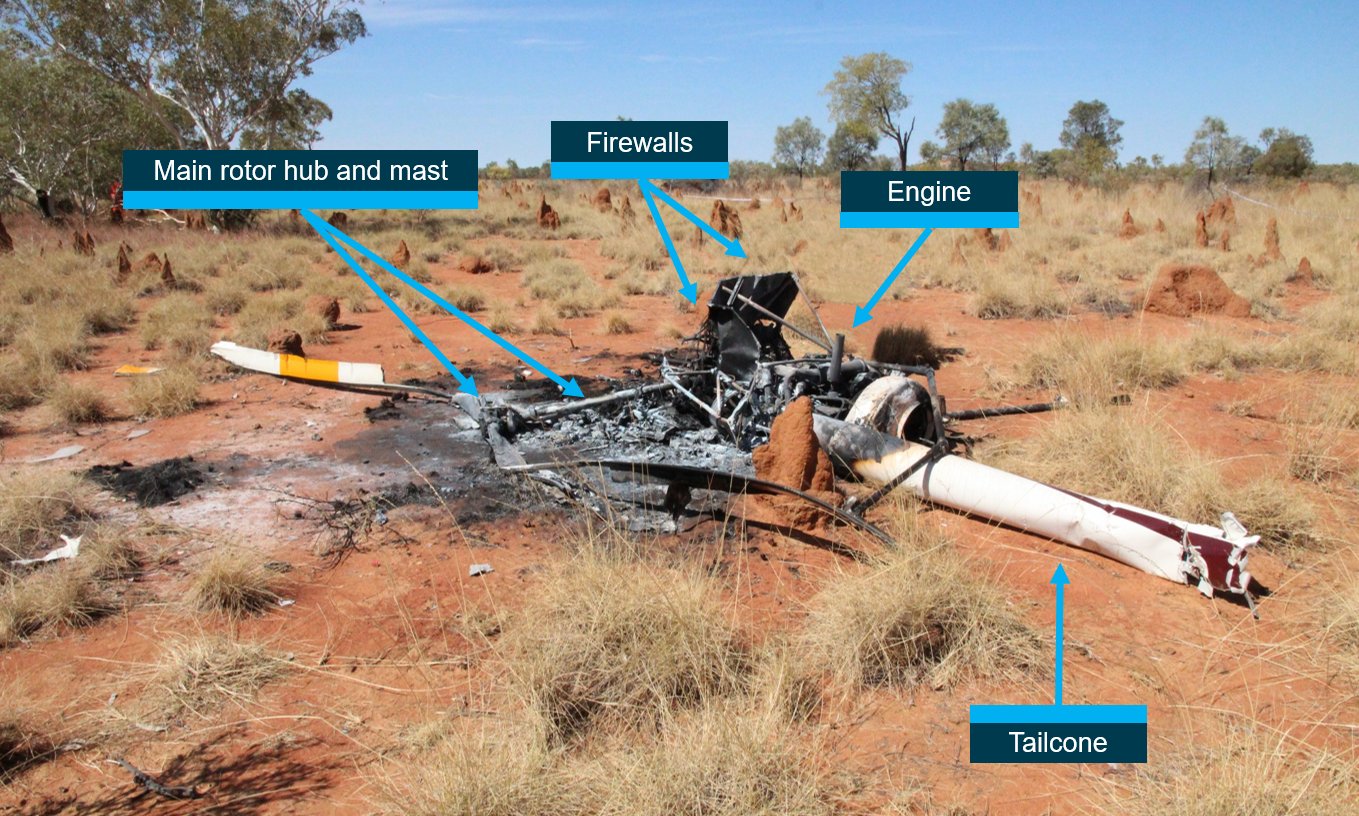
Figure 5: Main wreckage.
Source: ATSB

Source: ATSB

The airframe impacted the ground on the front left. Compression damage to the forward vertical firewall of the helicopter indicated that it impacted with a high rate of descent.

The helicopter’s main rotor disc had severed the tailcone and tail rotor driveshaft, leaving paint transfer on the driveshaft and tailcone. There were multiple strikes to tail components, which included the tail rotor hub and vertical stabiliser, generating a pattern of tail strike debris. The pattern was noted to be in a semi-circular arc on the right side of the main wreckage with respect to the direction of the GPS track. This was consistent with the helicopter tracking away from the airport and towards the powerlines at the time of the tailcone strike.

The main rotor blades exhibited rearward and upward bending, and there was no evidence of rotor blade ground strike marks or damage to the surrounding termite mounds. This was consistent with a significant loss of main rotor energy before ground impact, which was a near vertical impact. The teeter stops were destroyed by fire, but one teeter stop bracket was damaged and the associated main rotor blade spindle tusk[24] had a slight bend. This indicated the teeter stop bracket was struck by its respective main rotor blade spindle.

There was no evidence of any significant tension on the tail rotor driveshaft aft flexible coupling and little evidence of bending on the severed aft section of driveshaft (Figure 6). This indicated it was likely a power-on, high energy, main rotor strike to the tail.[25] The section of driveshaft forward of the severed section exhibited elongation and a bending overload, which indicated it was rotating during the break-up sequence. Therefore, the damage to the driveshaft was consistent with the main rotor disc striking the tail under normal engine power and rotor speed conditions.

Figure 6: Severed tail rotor driveshaft
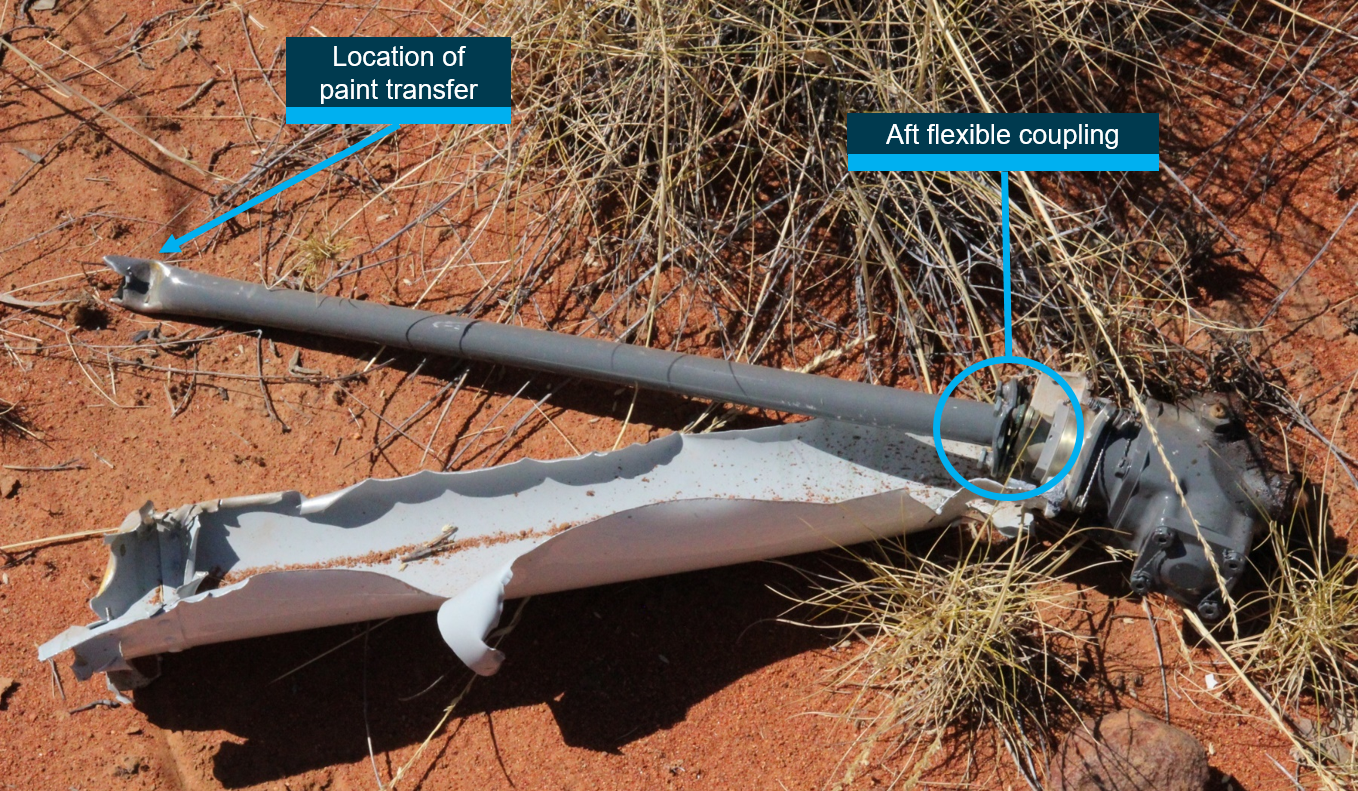
Figure 6: Severed tail rotor driveshaft.
Source: ATSB

Source: ATSB

The forward flexible coupling of the driveshaft exhibited significant tension. According to RHC, flexing of the main rotor mounts will change the angle of the input yoke of the main gearbox, which will cause the yokes at the flexible couplings to move apart. The tension on the forward flexible coupling, damage to the teeter bracket, and angle of the tailcone strike were consistent with a large rearward tilt of the main rotor disc in-flight past its normal limits.

On completion of the ATSB’s initial onsite inspection, the operator and next-of-kin buried the wreckage adjacent to the impact site.

Excavation

During the photographic review of the wreckage after the initial on-site inspection, the ATSB noted an anomaly with a flight control bellcrank (part number A958-1) in the cyclic control assembly. The fastener,[26] which attached the horizontal push-pull tube (part number A121-1) to the bellcrank, was missing. The remaining bellcrank fasteners were all attached. The missing fastener was part of the longitudinal cyclic control, which controls the fore-aft tilt of the main rotor disc (Figure 7). The RHC R22 Illustrated Parts Catalog (IPC) showed that the flight controls should be secured at the bellcrank with a National Aerospace Standard (NAS) 6604-15 bolt and D210-4 self-locking nut.[27]

Figure 7: Longitudinal cyclic control
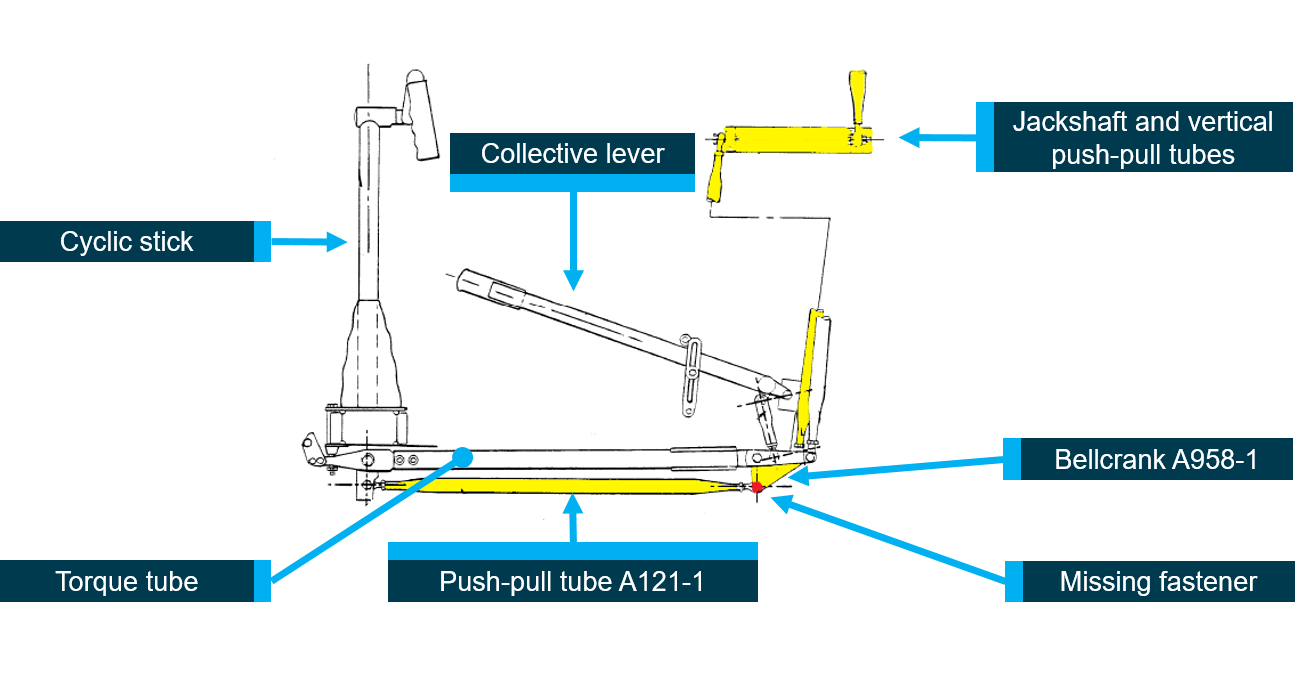
Figure 7: Longitudinal cyclic control.
Source: Robinson Helicopter Company, modified by the ATSB

Source: Robinson Helicopter Company, modified by the ATSB

The ATSB returned to Cloncurry in February 2018, and with the assistance of the pilot’s next‑of‑kin, the next of kin’s support persons, and the Cloncurry State Emergency Service personnel, excavated the majority of the buried wreckage and retrieved the bellcrank minus the missing fastener hardware. In addition to the bellcrank, the ATSB retrieved several pieces of resolidified metal to examine for the presence of hardware (bolt, standard washer, lockwasher, rod-end and self-locking nut).

In May 2018, the next-of-kin, who had continued excavating the remainder of the wreckage, sent a bolt with the same part number as the missing bolt (NAS6604-15) to the ATSB.[28] Following receipt of the bolt, the ATSB, in consultation with RHC and the next-of-kin, verified that all the remaining NAS6604-15 bolts were still attached to their respective assemblies.[29] This included the bolts not identified in the IPC as they are not normally accessible. As such, the bolt recovered from the excavated wreckage was considered very likely to be from the missing fastener. Figure 8 depicts the bellcrank and bolt.

Figure 8: Bellcrank with missing fastener (left) and bolt (right)

Figure 8: Bellcrank with missing fastener (left) and bolt (right).
Source: ATSB (left) and next-of-kin (right)

Source: ATSB (left) and next-of-kin (right)

Effect of loss of longitudinal cyclic control

The ATSB enquired with RHC about the expected response of the main rotor system to a disconnection of longitudinal cyclic control. They advised that:

During straight and level flight the A121-1 push-pull tube is under compression load. This pushes the cyclic aft [pilot’s cyclic stick]. A bungie cord is attached to the forward end of the tube (pulling aft, below the cyclic pivot point) to counteract the forces and neutralizes the loads felt by the pilot. The loads increase with airspeed.

With reference to Figure 7, a compression load on the A121-1 push-pull tube is consistent with a force tilting the main rotor disc aft and pushing downwards on the aft vertical push-pull tube. In forward flight, the advancing main rotor blade is at a higher airspeed than the retreating blade, which increases the lift on the advancing blade relative to the retreating blade. The reaction to this dissymmetry of lift is that the advancing blade flaps up and the retreating blade flaps down, which the pilot corrects with forward cyclic input as airspeed increases (Wagtendonk, 2011). Therefore, a disconnection of the longitudinal cyclic control in forward flight will result in the rotor disc tilting aft, potentially striking the tailcone.

Tests and research

Following identification that the rear fastener for the cyclic assembly horizontal push-pull tube was missing from the bellcrank, a number of items were recovered from the accident site and retained for further examination at the ATSB’s technical facilities in Canberra. The items included:

  • the bellcrank – part number A958-1
  • a bolt – part number NAS6604-15 (recovered by the next-of-kin on 16 May 2018)
  • metallic debris (that had melted during the post-accident fire then resolidified on cooling)
  • a number of loose nuts and washers
  • a jackshaft – part number A337-1 – including attachment nuts and bolts
  • the forward support assembly – part number A014-6.

A summary of the main findings from the examination is provided here, for full details of the examination refer to Appendix A – Materials examination report. The scope of the examination was to analyse the bellcrank and related components to determine how the fastener came to be missing. In addition, the metallic debris recovered from site was examined to determine if any additional fastener parts were entrapped within the solidified mass.

Bellcrank and related components

The bellcrank and torque tube yoke assembly had been subject to significant mechanical damage such that the rod ends had fractured in overstress and the left side of the yoke assembly and bellcrank plate had significantly distorted. While the distortion of the plates was similar where the fasteners remained in position, the plates had been pushed together where the fastener was missing (Figure 9). The yoke assembly also exhibited heat damage in this area, with the left side moulding around the bellcrank plate. The combination of mechanical and heat damage meant that an exemplar bolt could not be reinserted through the bellcrank.

Figure 9: Bellcrank showing deformation observed on the torque tube yoke assembly and bellcrank plates
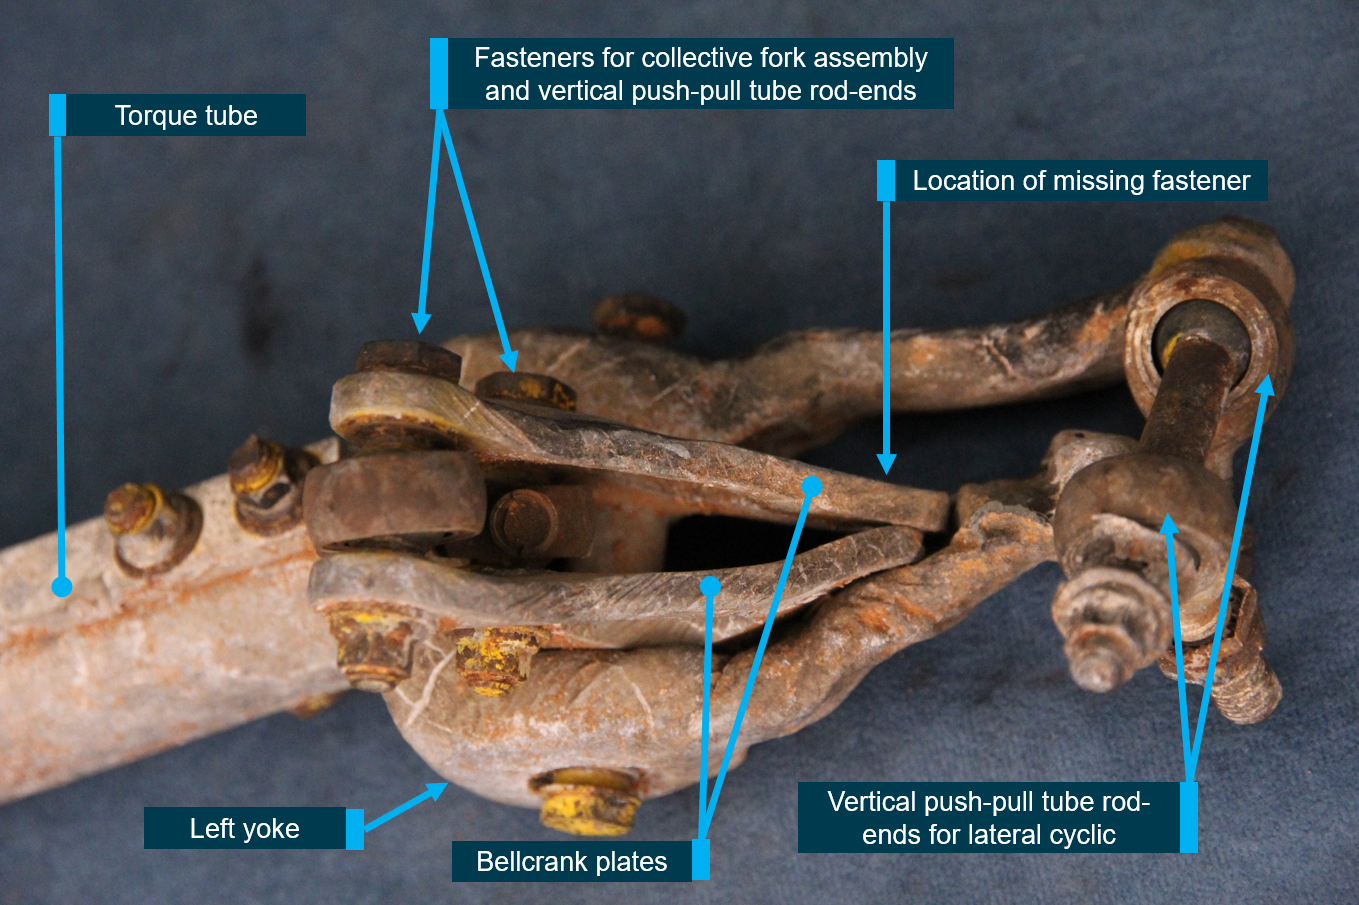
Figure 9: Bellcrank showing deformation observed on the torque tube yoke assembly and bellcrank plates.
Source: ATSB

Source: ATSB

The bolt holes where the fastener was missing did not exhibit gross deformation or elongation of the holes to indicate that the fastener assembly had been forcibly removed during the accident sequence. Yellow colouration was observed around the other bolt holes where the fasteners had remained in position. While some yellow colouration was observed around the bolt hole of the missing fastener, it was much less than for the other holes, and none was observed around the internal surfaces of the hole (Figure 10).

Figure 10: Bellcrank internal surfaces with yellow colouration
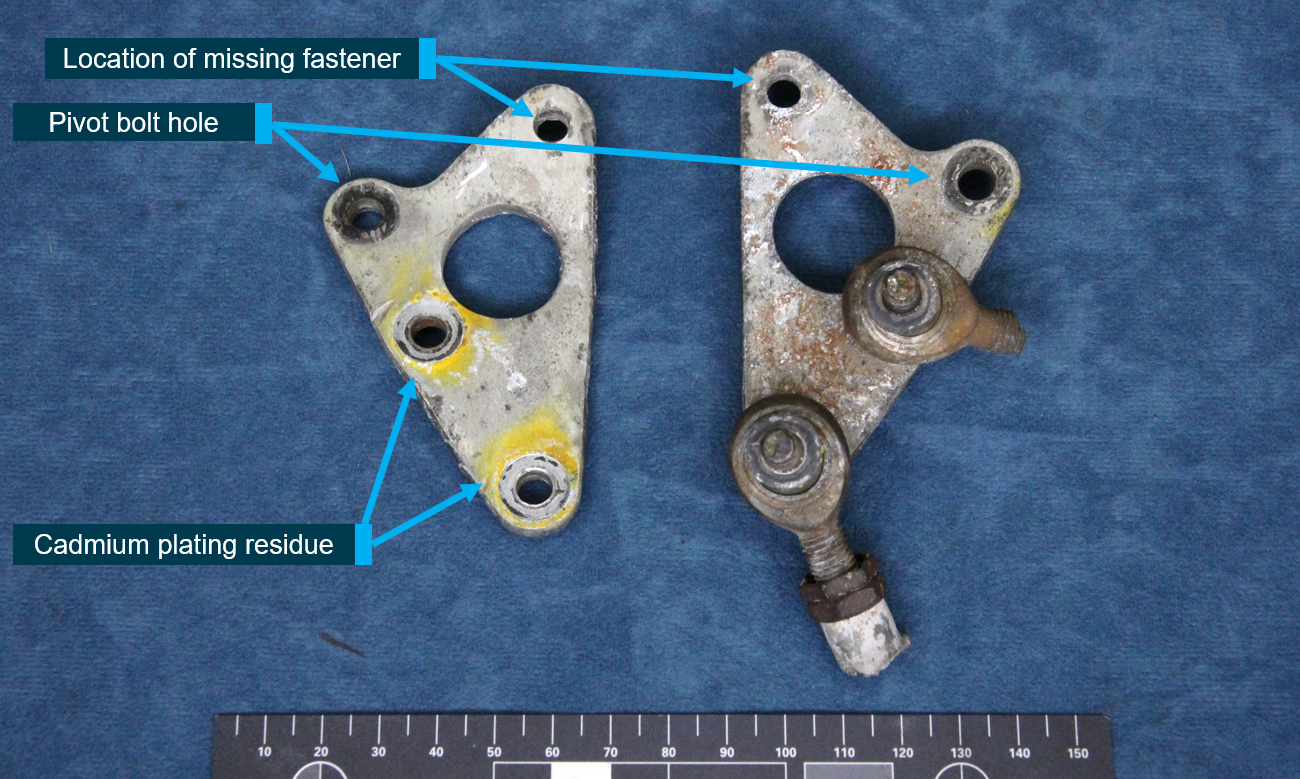
Figure 10: Bellcrank internal surfaces with yellow colouration.
Source: ATSB

Source: ATSB

Robinson reported that the yellow residue surrounding the fasteners was from the cadmium plating on the bolts, washers and screws.[30] The remnants of cadmium plating from the fastener assembly components had melted and subsequently oxidised during the post-accident fire. The residue surrounding the bolt hole for the missing fastener indicated the missing bolt was previously torqued, resulting in a transfer of cadmium from the washer to the bellcrank. However, as there was no outward flow, or streaking, as per the remaining fasteners, RHC considered it ‘highly unlikely that the missing bolt was present during the fire’.

The combination of the above observations indicated that the missing bolt was not fitted to the bellcrank at the time of the impact with terrain and post-impact fire.

The remaining two bolts installed on the bellcrank were identified as NAS6604-15 bolts and the nuts were consistent with the MS21042L4/NAS1291 nut-type with manufacturer markings consistent with Ronson Manufacturing Inc.

Metallic debris

The metallic debris was dissolved, and a number of fasteners and other components were recovered. However, examination of the pieces did not identify any parts from the missing fastener.

Recovered bolt

The solitary bolt found on 16 May 2018 by the next-of-kin was identified as a NAS6604-15 bolt. The bolt had the same manufacturer identification (‘LFC’) as the other two bolts fitted to the bellcrank, but exhibited greater fire damage (Figure 11).

Figure 11: Comparison between the bolts removed from the bellcrank (left and centre) and the fire damaged bolt (right) subsequently recovered from the accident site

Figure 11: Comparison between the bolts removed from the bellcrank (left and centre) and the fire damaged bolt (right).
subsequently recovered from the accident site.
Note: The recovered bolt is shown after it had undergone ultrasonic chemical cleaning.
Source: ATSB

Note: The recovered bolt is shown after it had undergone ultrasonic chemical cleaning.

Source: ATSB

The recovered bolt was thermally damaged from the post-accident fire, but was otherwise in good condition with no evidence of distortion along its length or to the threads. A small groove was identified on the thread flank, which was likely from contact with a self-locking nut during installation (Figure 12).

Figure 12: Magnified image of the bolt found 16 May 2018 showing thread groove

Figure 12: Magnified image of the bolt found 16 May 2018 showing thread groove.
Source: ATSB

Source: ATSB

Jackshaft

Examination of the jackshaft assembly recovered from the wreckage found that three of the four self-locking nuts had the same manufacturer markings as the nuts fitted to the bellcrank. Fire damage precluded identification of the markings on the fourth nut.

Semi-quantitative chemical analysis of the nuts was conducted using a scanning electron microscope equipped with an Oxford energy dispersive x-ray spectrometer. The analysis confirmed that all four nuts were consistent with a carbon/alloy steel. While the spectrometer cannot determine the exact amount of alloying additions, the spectrographs for the four nuts were inconsistent with the CRES (corrosion resistant – stainless steel) D210-4 nuts specified to be used by RHC. Specifically, the nickel, chromium and molybdenum additions, where detected, were not of sufficient quantities to designate the nuts as stainless steel (see Previous safety issues - self-locking nuts).

Maintenance of the cyclic control assembly

During their interviews with the ATSB in 2018, the CAM staff[31] could not recall the specific details of the work they individually performed on the cyclic control system of VH‑HGU during the 2,200‑hour overhaul. However, they were able to provide a description of the normal process they followed for the removal, inspection, installation and inspection of the cyclic control assembly. The physical process, as described by CAM staff, was consistent with the process published and described by RHC.

Removal

The removal process involved the vertical push-pull tubes being unscrewed from the bellcrank and yoke rod-ends, then the remaining components from the cyclic stick through to the bellcrank would be removed from the airframe as a single unit. After removal from the airframe, the length between the bolt holes for the horizontal push-pull tube would be measured for use during reassembly. There was no record of this measurement in the work-pack for VH-HGU, however, the maintenance manual provided a standard length that could be used for the installation.

The horizontal push-pull tube forward fastener would then be disconnected from the cyclic stick and the horizontal push-pull tube unscrewed from the bellcrank rod-end. Therefore, the bellcrank fasteners were not required to be disassembled during this part of the process. The cyclic stick is separated from the torque tube, but the bellcrank can remain attached to the torque tube with the fasteners and rod-ends fitted, as neither of these components required non-destructive testing.

Inspection

The bellcrank is inspected for cracks and corrosion, and the rod-ends are tested for axial and radial play (Figure 13). According to RHC, the play in the rod-ends can be checked without removal from their respective fastener. The CAM staff reported that the rod-ends would initially be checked for play without their removal, and then only removed for measurement with a dial test indicator if there was doubt. The chief engineer reported that the rod-end would be replaced if it had reached half the permitted tolerance as the wear will accelerate and it was preferable to replace them at the 2,200-hour overhaul, rather than at a 100-hour inspection.

Figure 13: Rod-end and spherical bearing play limits
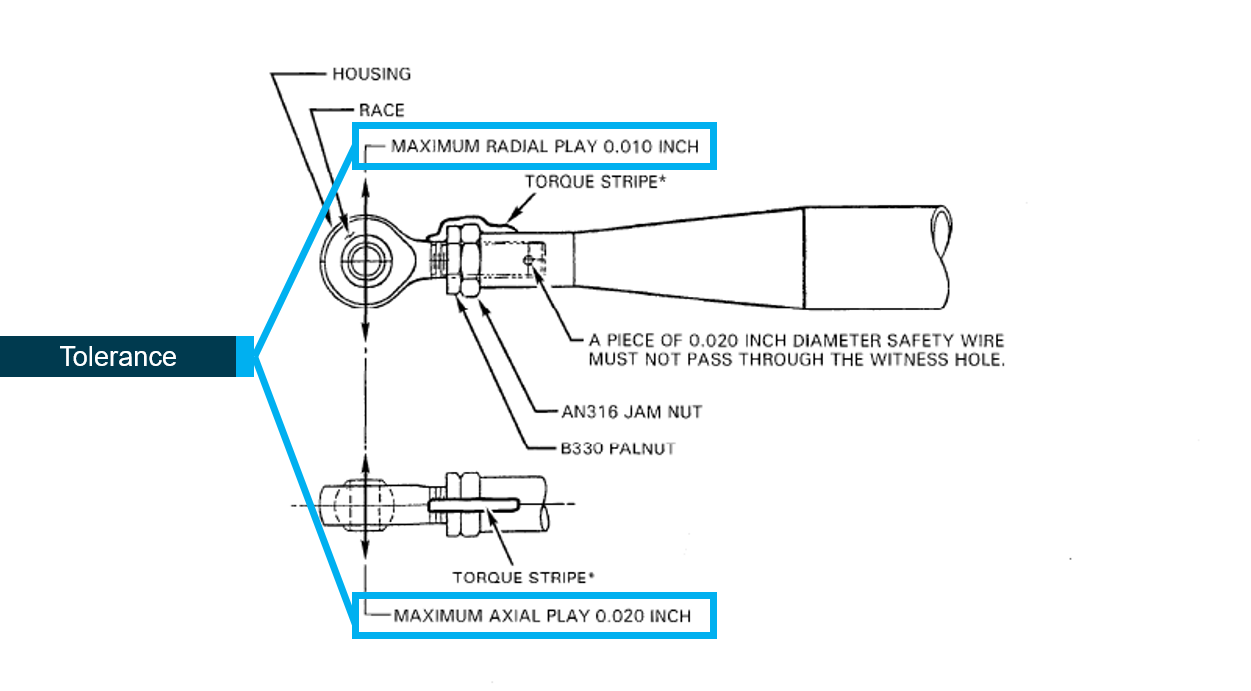
Figure 13: Rod-end and spherical bearing play limits.
Source: Robinson Helicopter Company, annotated by the ATSB

Source: Robinson Helicopter Company, annotated by the ATSB

There was no record in the work-pack to indicate that any of the bellcrank rod-ends were replaced or disturbed for inspection. However, other than what the maintenance manual specified for the overhaul, disturbances of the flight controls were not recorded in the work-pack unless a part was replaced. Several rod-ends from other assemblies were replaced during the overhaul, and they were accounted for by a cross-check between the ‘parts list’ and ‘aircraft worksheet’ sections of the work-pack.

Installation

After removal and disassembly, the push-pull tubes and cyclic stick would then be stripped of their paint and sent for non-destructive testing. All parts for VH-HGU were found serviceable from non‑destructive testing, and on return, they were painted and re-assembled. One of the apprentices reported the cyclic assembly could be removed and installed by an individual, but it was more common to use two persons, ‘depending on what was going on’. In August 2017, the chief engineer could not recall who refitted the parts returned from non‑destructive testing. The installation was certified as having been performed by the AME (aircraft maintenance engineer). However, in February 2018, the AME could not remember anything about this work.

The AME reported that the chief engineer would normally inspect the cyclic when re‑assembled, and again when it was installed. After installation, the chief engineer would assist the AME with the rigging process and then perform an ‘inspection and make a list and get them to fix it… and then get [head engineer] in to check’. The fourth year apprentice was reportedly involved in the disassembly, reassembly and rigging, but was unsure about the first year apprentice’s involvement. The first year apprentice was reportedly involved in the disassembly, but was at trade school 1–13 July 2017, and missed some of the reassembly.

According to RHC, if the cyclic assembly is installed and the horizontal push-pull tube has the incorrect length between bolt holes, then it is easier to remove the aft rod-end (bellcrank fastener) to make the length adjustment. However, this is most likely to be discovered during the rigging process and compensated for by adjusting the vertical push-pull tube lengths or pitch links, unless it is excessively far from the specified dimension. The chief engineer reported that for the rigging adjustments they ‘generally do it on the upper push-pull tubes—wind them all the way in and then adjust at the top—sometimes the lower push-pull tube, but don’t recall having any trouble with the accident helicopter’.

The head engineer reported that the cyclic assembly fasteners are torqued and torque striped[32] before the assembly is installed, which is when the independent inspections for correct assembly would be performed. After installation, the head engineer would perform an independent inspection for correct fitment and clearances. The head engineer would then provide a list of discrepancies to the chief engineer, and then re‑inspect after any adjustments had been made. As the work-pack was not used to record discrepancies and adjustments, it could not be determined if any discrepancies were found or if any adjustments were performed.

100-hour inspection

After the helicopter had been assembled and the flight controls rigged, the next step in the overhaul procedure was for a 100-hour inspection to be performed. For VH-HGU, this inspection was certified by the AME and chief engineer using a CAM form, which was a one-page abbreviated checklist. The CAM checklist condensed the RHC R22 maintenance manual certification requirements from 226 items to 19 items. Consequently, each item in the CAM checklist accounted for between 1-30 separate inspection items. However, the CAM checklist specifically stated that the 100-hour inspection checklist was to be used in conjunction with RHC maintenance manual.

Figure 14 shows a comparison of the CAM checklist item (left) with the RHC R22 maintenance manual (right) for the removal of the horizontal cover cyclic box cover, belly panel and vertical panel. The depiction below of the maintenance manual is one of three pages under the heading 4 task certifications. Inspection of the cyclic push-pull tubes, bellcrank and fasteners were items 19, 20 and 26. These items were covered as item 4 in the CAM abbreviated checklist.

Figure 14: Comparison of the CAM 100-hour inspection checklist (left) and the R22 maintenance manual (right)
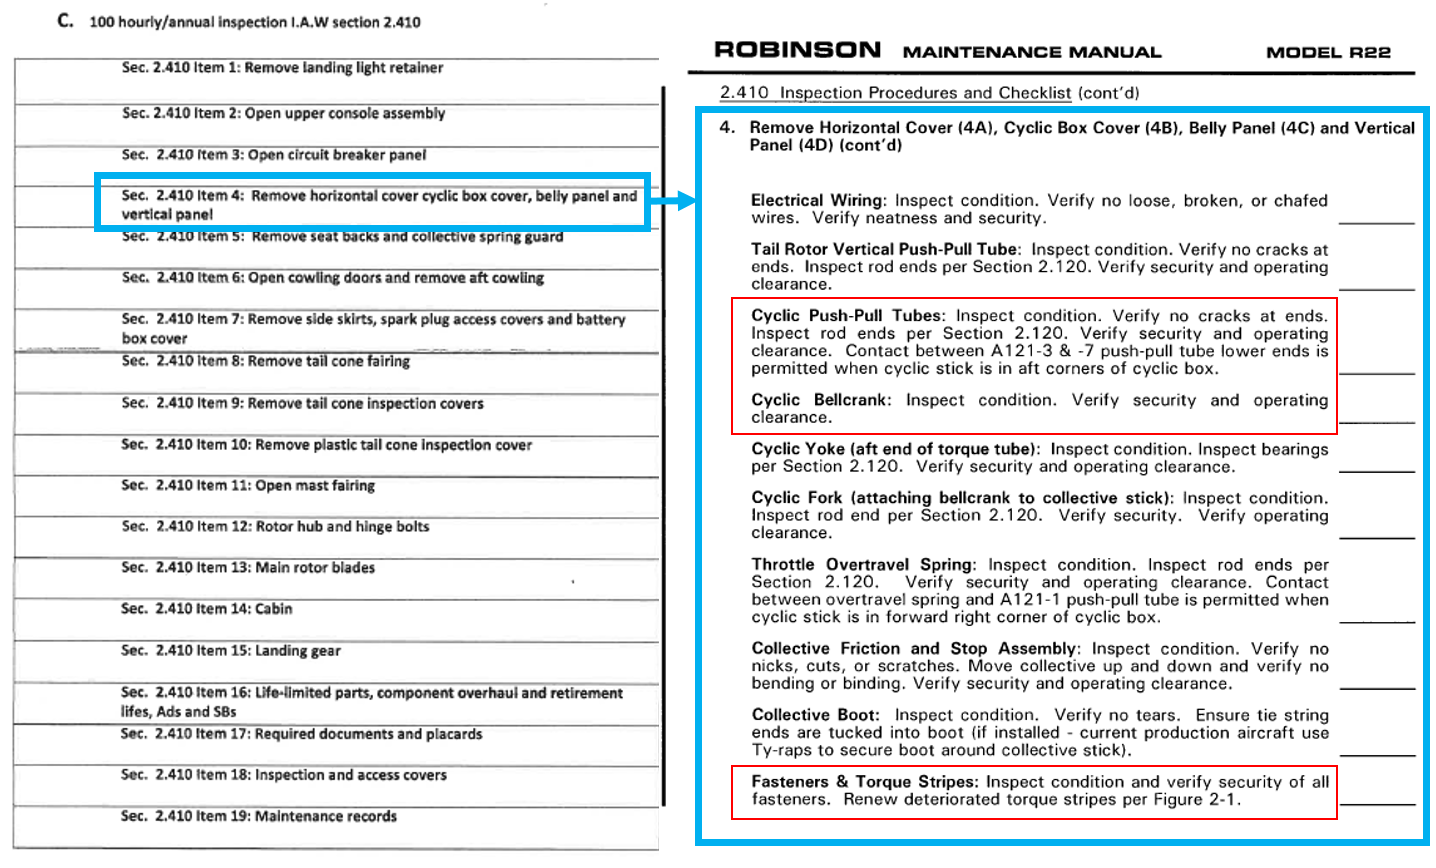
Figure 14: Comparison of the CAM 100-hour inspection checklist (left) and the R22 maintenance manual (right).
Source: Cloncurry Air Maintenance (left) and Robinson Helicopter Company (right), annotated by the ATSB

Source: Cloncurry Air Maintenance (left) and Robinson Helicopter Company (right), annotated by the ATSB

Certification for the work

Item 18 of the CAM checklist was for the installation and closure of all access panels on completion of the 100-hour inspection. At interview in August 2017, the chief engineer reported that the certification for independent inspections was after the rigging, but before the panels were installed and the fuel tanks calibrated. However, the work-pack suggested that the fuel calibration was recorded before certification for independent inspections, which was the last entry in the ‘aircraft work-sheets’ section of the work-pack.

At the completion of the 100-hour inspection, the helicopter was to undergo a ground run, track and balance of the main rotors, autorotation RPM check and flight check. The work-pack showed that the AME certified for the ground check and run-up, a fanwheel and tail rotor balance, the track and balance of the main rotor and autorotation RPM check.

Of note, the AME was not qualified to ground run the helicopter, and the pilot for the track and balance flights was reportedly following the chief engineer’s instructions for the flights, not the AME. The pilot and chief engineer both reported that several flights were required for the track and balance of the main rotor, with adjustments made between the flights.

No entries in the work-pack were found for any track and balance adjustments, or for the check flight, which was required to follow the track and balance, and autorotation RPM check flights. The chief engineer reported that they were not using the maintenance manual checklists for these steps of the overhaul procedure. Instead, loose paper was used, which was not retained in the work-pack. Therefore, it was unknown what adjustments were made to the helicopter.

The work-pack showed that the AME certified for all the tasks in the aircraft work-sheets on 31 July 2017 and the chief engineer certified for the supervision on the same date.[33] Although there was no date recorded for the certification for independent inspections, it was considered likely that it was on the same date as this was the last entry in the work-sheets. Similarly, the 100‑hour inspection certification was also not dated, but considered likely to have also occurred on the same date.

The ATSB noted that the single date certification at the end of the overhaul was not in accordance with the CAM Maintenance Procedures Manual (MPM). The MPM Part 6.10: Scrutiny of Work and Certification, required progressive certification for each ‘item as it is completed on the work package’.

Organisational and management information

Organisational structure

Cloncurry Mustering Company’s primary operations were cattle mustering and other airwork from their main base at Cloncurry Airport. The majority of maintenance conducted on their fleet of 23 R22 and four R44 helicopter’s was performed by CAM, which was an associated company. In addition to this, CAM also performed work on external helicopters for other operators.

The facilities in Cloncurry were used by both CAM and CMC, and they had the same managing director (MD) and shareholders. The shareholders included the MD, chief engineer and several of the CMC senior pilots, including the accident pilot. The chief engineer for CAM also held the position of maintenance coordinator [34] for CMC.

One of the key positions in an operator’s organisational structure is the Head of Aircraft Airworthiness and Maintenance Control (HAAMC). The position of HAAMC provides an interface with maintenance organisations for the planning and preparation of maintenance activities, and an independent check of the completion of those activities when an aircraft is returned to service.

The MD was issued with the CMC HAAMC approval by CASA in June 2005. According to the letter of approval, the HAAMC ‘has the responsibility for all airworthiness matters relating to the aircraft operated under the AOC [Air Operator Certificate]’. Within the CMC operations manual, the responsibilities of the HAAMC were delegated to the maintenance coordinator (chief engineer). The ATSB considered this a pragmatic decision, as the chief engineer was the individual most suitably qualified and experienced for the role and responsibilities. However, it resulted in the two key positions of interface between CAM and CMC for maintenance and airworthiness matters being held by the same person.

Cloncurry Air Maintenance

Maintenance approval

Cloncurry Air Maintenance had a Certificate of Approval for the maintenance of piston-engine helicopters with a maximum take-off weight not exceeding 3,175 kg. Their approval included the maintenance of airframe, engines, engine components, and electrical components fitted to, or eligible to be fitted to, R22 and R44 helicopters. In accordance with Civil Aviation Regulation 1988, Section 30, CAM had a documented set of quality control procedures, published as their Maintenance Procedures Manual (MPM).

Workforce

In 2013, the CAM workforce comprised of four licenced aircraft maintenance engineers (LAMEs) and two apprentices. By the time of the accident, in August 2017, the workforce structure had changed to two LAMEs (the chief engineer and head engineer), one AME and three apprentices. All of these employees had been trained by CAM from the time of their apprenticeships.

The division of work for CAM required the chief engineer to manage the CMC helicopters, while the head engineer managed the external helicopters. The two LAMEs would support each other for independent inspections, with the chief engineer certifying for the independent inspections of external helicopters, and the head engineer certifying for the independent inspections of CMC helicopters. The AME and two apprentices were allocated to the CMC helicopters and the third apprentice allocated to support the head engineer working on the external helicopters. The two apprentices working on the CMC helicopters were a first year and fourth year apprentice. The first year apprentice was required to attend trade school and therefore not always present.

The chief engineer reported that it was difficult to recruit a LAME workforce into Cloncurry, due to its remote locality, and that alternative apprenticeship schemes might be perceived as less demanding with more attractive remuneration. The MD believed that the LAME recruitment problem was not limited to their business and that it was a wider problem, which also affected businesses on the east coast.

Workload

The cattle mustering season from April to September required an increase in the maintenance workload through the middle of the year to keep the CMC helicopters operating. The CAM hangar space facility was divided between a main area, where several helicopters could be parked for 100-hour inspections, and two separate 2,200-hour overhaul rooms dedicated for one CMC helicopter and one external helicopter.

At interview, none of the maintenance staff could recall any specific details associated with the disassembly and reassembly of the cyclic control assembly during the overhaul on VH-HGU. All staff reported it was a busy period and that the overhaul was routinely interrupted for 100-hour inspections. In the month of July 2017, 21 100-hour inspections were commenced on CMC helicopters and 20 were completed, in addition to progressing the overhaul of VH-HGU to completion on 31 July (plus one external helicopter in overhaul).

Robinson reported that a 100-hour inspection should take about 24 labour-hours to complete. Therefore, to complete 20 inspections in the month of July would require about 480 labour‑hours. This would have required about three qualified staff (LAME/AME) working full time on the 100 hour-inspections for CMC helicopters, plus additional staff to progress the overhaul of VH-HGU. A calendar break-down of the 100-hour inspections and 2,200-hour overhauls for the CMC helicopters over the months of July and August is provided at Appendix B – Maintenance workload.

Quality assurance

Internal audits

Part 8 of the CAM MPM described the purpose of their internal audit program was:

…to ensure that the effectiveness and performance of the Company and the procedures documented in the Maintenance Procedures Manual are continually being measured and assessed.

As they did not have a quality manager position, and none was required, CAM contracted an external auditor to perform their internal audits. The ATSB reviewed the two internal audit reports produced for CAM in 2015 and 2016, and noted that each had been performed by a different auditor.

The December 2015 audit included a review of three work-packs and ‘nil findings’ were recorded against them. The November 2016 audit included a review of one work-pack and ‘nil defects’ were recorded. Both audit reports concluded with ‘nil non-conformances’, ‘nil requests for corrective action’ and ‘nil suggestions for system improvement’.

The work-pack sampled for the 2016 audit was for an R22 100-hour inspection. The ATSB reviewed this and noted the CAM 100-hour inspection abbreviated checklist was used and that all work was certified on the same day as performed by one LAME. In this instance, a single certification was provided for the ground check, run up and all 19 items on the abbreviated checklist.

Civil Aviation Safety Authority oversight

The CASA Cairns office was responsible for oversight of CAM. In the period from June 2013 to January 2018, 22 entries were made in the CASA database for their oversight of CAM. They included nine references to ‘nil’ or ‘no major issues’ and five references to CAM as a ‘compliant organisation’

On 13 May 2015, an audit was conducted on CAM by one CASA airworthiness inspector for one day. On 22 June 2015, the auditor entered into the database for CAM ‘recent audit carried out on Western Planes [plains] Sweep – compliant organisation’. The May 2015 visit was their last audit of CAM prior to the accident on 2 August 2017.

2015 audit

In the May 2015 CASA audit report summary, the auditor reported that CAM ‘was assessed against the regulatory requirements within the system listed below (scope)’. The elements included:

  • maintenance activity
  • data and documents
  • tooling and equipment
  • stores and distribution.

The auditor assessed CAM compliance against the MPM and did not identify any breaches of the regulations. Two observations were issued as opportunities for improvement.[35]

The audit report stated that:

Control of Maintenance Activity was assessed compliant when audited against Chapter 6 of the MPM. The Chief Engineer is conducting all duties as detailed in the MPM and controls the company workpacks and maintenance activities.

Sampling was conducted on three workpacks…with no issues identified.

The ATSB obtained a copy of the 2,200-hour overhaul work-pack sampled by the auditor. This was for an R22 helicopter, for which the overhaul was completed in 2015. The work-pack omitted several steps of the overhaul procedure, specifically, there were no entries for the 100-hour inspection, ground run, run up and check flight. While the track and balance was recorded and certified in the work-pack, there were no records for any adjustments. The entire work-pack was certified with a single date, which indicated progressive certification was not employed as required by the CAM MPM.

The auditor’s notes did not reveal any further information about the CAM audit than what was recorded in the report. However, of note, the auditor did not retain copies of the work-packs sampled. Instead, the auditor’s notes included photographs of the front pages of the work-packs. The report was certified by the auditor and approving officer on 25 May 2017.

2018 audit

After the accident, on 10–11 April 2018, CASA conducted an unscheduled Level 1 surveillance audit of CAM. The team comprised one airworthiness inspector and one engineering officer. During the course of the CAM audit, several findings were identified as airworthiness matters. This resulted in the expansion of the scope of the audit to include CMC.

The expansion of the scope resulted in CASA issuing two reports, one for CAM (the maintenance organisation) and one for CMC (the operator). The audit sampled several work-packs, which included the 2,200-hour work-pack for the R22 helicopter that started overhaul on 1 August 2017. The auditors made similar findings to what the ATSB noted for the work-pack for VH-HGU and the CASA 2015 audit of CAM. They included the following issues:

  • Use of abbreviated checklists: The certification points in the company abbreviated 100-hour inspections checklists did not reflect the content of the inspection items listed under them in accordance with the RHC R22 maintenance manual. The use of abbreviated checklists relied on the maintenance staff continually referring to the maintenance manual to identify all the inspection items under each heading. The inspectors recommended CAM review the suitability of using abbreviated inspection checklists.
  • Independent inspections: The 2,200-hour work-packs sampled found one independent inspection performed at the end of the overhaul. Given the scope of the overhaul and level of disassembly, reassembly and adjustments required, the auditors recommended that independent inspections are certified progressively and noted that additional inspections would be required for each adjustment of flight control components during the tracking and balancing procedure.
  • Flight without a maintenance release: The chief engineer confirmed that it was their standard procedure to complete the flying tasks within the 2,200-hour overhaul before issuing a new maintenance release. Therefore, the helicopters were being flown without a valid maintenance release.
  • Maintenance coordinator responsibilities: A number of helicopters were released to service without complying with their approved maintenance program. The CMC operations manual required the maintenance coordinator check all maintenance was completed before an aircraft was returned to service.

Previous occurrences involving fasteners

CASA R44 service defect report

On 17 May 2018, another operator’s Robinson R44 helicopter completed a 2,200-hour overhaul, which included the replacement of the flight control hydraulic servo assemblies. The overhaul was certified by a LAME and with an accompanying independent inspection certification. On 26 February 2019, the operator submitted a service defect report to CASA following a pilot report of ‘deterioration of flight control inputs along with banging sound coming through airframe’.

On inspection, the bolts used to secure the hydraulic servos to the support bracket were found to have insufficient torque. The MS21042L-series nuts had not been replaced with D210-series nuts (see Re-use of self-locking nuts below), and no Palnuts®[36] were fitted as secondary locking devices in accordance with the instructions for continued airworthiness. The inadequate torque allowed movement of the servos, which resulted in elongation of the NAS6600-series bolts and the bracket bolt holes. Of note, despite the insufficient torque and elongation of the bolts, the MS21042L-series self-locking nuts fitted to the bolts had not failed or undone.

United States National Transportation Safety Board (NTSB/AAR-13/01)

On 7 December 2011, a Eurocopter AS350-B2 helicopter, operating as a ‘Twilight tour’ sightseeing trip, crashed in mountainous terrain about 14 miles east of Las Vegas, Nevada. The pilot and four passengers were fatally injured, and the helicopter destroyed. The United States National Transportation Safety Board (NTSB) found that the accident was a result of an in-flight disconnect of the flight controls, specifically, the separation of the servo control input rod from the main rotor fore-aft servo, which rendered the helicopter uncontrollable. The bolt, washer, self‑locking nut, and split pin that normally secured the input rod to the fore-aft servo were not found. It was concluded that the hardware had been improperly secured during maintenance the day before the accident

The NTSB found there was inadequate maintenance of the helicopter, including (1) the improper reuse of a degraded self-locking nut, (2) the improper or lack of installation of a split pin, and (3) inadequate post-maintenance inspections. They reported the contributing factors included personnel fatigue for the mechanic and inspector, and the lack of clearly delineated maintenance task and inspection steps.

ATSB investigation AO-2011-135

On 12 October 2011, the pilot of a Robinson R22 helicopter, registered VH-JNP, was performing aerial work near Saxby Downs, Queensland, when a rattling noise from behind the cabin was heard by the pilot, who also noted the clutch light had illuminated. The pilot opened the clutch actuator circuit breaker and, at the same time, noted a burning rubber smell. The pilot made an immediate precautionary landing and shut down the helicopter.

The problems with the helicopter’s drive system were traced to the clutch assembly where a group of MS21042L-4 self-locking nuts on the drive belt upper sheave had cracked and fractured. This premature nut failure had stemmed from the likely embrittling effect of residual hydrogen generated during the cadmium electroplating process applied during manufacture. All of the affected self-locking nuts were identified as Airfasco Industries Fastener Group (affected batches identified as 12 June 2009, 23 October 2009 and 19 October 2010). They were fitted in April 2011, at the last 2,200-hour overhaul. Since that time, the helicopter had operated for a further 408 hours and was subject to four 100-hour inspections during that period.

ATSB investigation AO-2011-016

On 4 February 2011, a Robinson Helicopter Company R44 Astro helicopter, registered VH‑HFH, commenced circuit operations at Cessnock Airport, New South Wales. Following a landing as part of a simulated failure of the hydraulic boost system for the helicopter’s flight controls, the instructor elected to reposition the helicopter to the apron. As the helicopter became airborne, it became uncontrollable and collided with the runway and caught fire. The pilot survived, but the instructor and a passenger were fatally injured.

The ATSB found that a fastener had detached from a hydraulic-boost servo, rendering the helicopter uncontrollable. The hydraulic-boost servo was repaired and functionally tested by the manufacturer in February 2009. The servo spent the majority of its time as a spare in storage before it was installed on VH-HFH in October 2010 during the last 100-hour inspection. The helicopter accrued 93.6 hours in-service prior to the accident. The bolt was recovered and noted that there was no distortion, and its threads and shank were visually undamaged. However, the remaining fastener parts were not recovered.

Previous safety issues – self-locking nuts

Hydrogen embrittlement

In the final investigation report of AO-2011-016, as mentioned above, the ATSB examined three cracked self-locking nuts from other R22 helicopters, of the same specification as that fitted to the detached fastener on the accident helicopter. These nuts were found to have cracked due to hydrogen embrittlement. Specifically, the report stated that:

When high-strength steel, which has been exposed to hydrogen is sufficiently stressed, it can fail prematurely in a sudden, brittle manner. In the case of the examined self-locking nuts, the source of hydrogen was likely to have been from the cadmium plating process that was specified during manufacture for corrosion resistance. Under conditions of sustained stress, such as that associated with an assembled fastener, plus any residual tensile stresses from manufacturing, the presence of hydrogen can result in brittle cracking, typically less than 1 week from the time of application of the sustained stress.

In response to the identification of the hydrogen-embrittled self-locking nuts, the ATSB raised the following safety issue (AO-2011-016-SI-01 – Self-locking nut failure) on 30 April 2012, affecting owners and operators of RHC helicopters:

A number of self-locking nuts from other aircraft, of the same specification as that used to secure safety-critical fasteners in VH-HFH, were identified to have cracked due to hydrogen embrittlement.

During the course of the investigation the ATSB was provided with three self-locking nuts from other aircraft that had cracked in service. Detailed examination of those nuts identified that they had failed due to hydrogen embrittlement. In response to that finding, the ATSB notified the helicopter manufacturer, the Civil Aviation Safety Authority (CASA) and the United States National Transportation Safety Board and Federal Aviation Administration.

At the time of publishing that investigation report and safety issue, RHC had reported the following proactive safety action in response to the safety issue:

In response to the identification of hydrogen-embrittled self-locking nuts during this investigation, the helicopter manufacturer issued service letters (SL-58, SL-38 and SL-01),[37] which detailed the hydrogen-embrittlement risk, including the expected failure characteristics.

The Civil Aviation Safety Authority also reported the following proactive safety action at the time of publishing:

In response to the identification of hydrogen-embrittled self-locking nuts, CASA issued Airworthiness Bulletin 14-002, on 12 October 2011, alerting aircraft owners, operators and maintenance personnel to the possibility of in-situ failures of MS21042 and NAS1291-series self-locking nuts. The bulletin provided background information on previous occurrences and the mechanism and hazards associated with hydrogen embrittlement, and recommended that:

Pilots and maintenance personnel closely monitor the occurrence of hydrogen-induced delayed cracking in high-strength steel standard aircraft hardware, such as nuts via close inspection following installation and thereafter at Daily / Preflight and periodic inspections.

Before simply replacing cracked/failed nuts with new items, consider contacting the manufacturer for advice regarding replacement of associated fasteners which may have suffered over-loading as a result of the failure of one of more nuts.

Report all MS21042 and NAS1291-series nut failures to CASA via the SDR [Service Difficulty Reporting] system.

Re-use of self-locking nuts

As explained above, cracking from hydrogen embrittlement of nuts fitted to Robinson helicopters has been previously identified.[38] In October 2014, RHC published service letters for the R22 (SL‑64), R44 (SL-50) and R66 (SL-09) helicopters on the subject of D210 Corrosion-Resistant (CRES) Nuts.[39] The service letters stated that, whenever maintenance that involves the disassembly and reassembly of a critical fastener is performed, the MS21042L or NAS1291-series nut should be replaced with a D210-series nut. The R22 maintenance manual was amended in October 2014 to incorporate what was stated in SL-64. For specific instances of cracked nuts, RHC have published service bulletins for their replacement within a compliance period.[40]

The R22-series maintenance manual included the following information under section 1.300 Fastener Torque Requirements:

D. Critical Fastener: A critical fastener is one which, if removed or lost, would jeopardize safe operation of the helicopter. This includes joints in the primary flight control system, and non-fail-safe structural joints in the airframe, landing gear, and drive system.

CAUTION: D210-series nuts, which supersede MS21042L-series and NAS1291-series nuts, are required on critical fasteners.

In the course of interviewing maintenance personnel employed by CAM, the ATSB noted a low‑level of awareness of the need to replace self-locking nuts with the D210-series nuts when critical fasteners were reassembled. However, the staff were aware of the limitation on the re-use of them, specifically, that they could not be reused if they had lost their friction torque. It is a standard practice within sectors of the aviation industry to re-use self-locking nuts provided the nut cannot be turned onto the bolt thread by hand and the published torque value for the fastener is achieved.[41]

During the course of the investigation, the ATSB spoke with another maintenance organisation, who reported that they employ the same practice of re-using self-locking nuts, and RHC confirmed that the described practice was considered acceptable. The United States NTSB reported on this practice as accepted by the manufacturers of light helicopters in their accident report AAR‑13/01.[42] They noted that guidance on the re-use of self-locking nuts was provided by Eurocopter (now Airbus Helicopters), Sikorsky, Bell and the United States Federal Aviation Administration.

In December 2018, the ATSB received the accident helicopter’s jackshaft, which had the fasteners attached. The jackshaft was one of a number of parts within the flight control system that was disassembled and sent for non-destructive testing during the 2,200-hour overhaul. The bellcrank was not subject to non-destructive inspection and therefore not required to be disassembled. In late January 2019, the ATSB completed semi-quantitative chemical analysis of the nuts fitted to the jackshaft and found they were consistent with a carbon/alloy steel, and therefore not consistent with D210-series stainless steel corrosion-resistant nuts. The nuts fitted to the jackshaft had similar markings to the nuts fitted to the bellcrank, which were consistent with MS21042L/NAS1291-series nuts.

At the time of the reassembly of the accident helicopter, the current R22 Illustrated Parts Catalog listed the part number D210-4 for the nuts fitted to the jackshaft, and RHC confirmed there were no alternate part numbers to the D210-series nuts.

In consideration of the evidence, the ATSB concluded that the industry practice of re-use of self‑locking nuts on Robinson helicopters may result in the omission to install D210-series nuts when critical fasteners are reassembled. Therefore, as part of this investigation, the ATSB issued a safety advisory notice (AO-2017-078-SAN-001) on 28 March 2019.

Memory-related errors

In the 2008 ATSB research report An Overview of Human Factors in Aviation Maintenance (AR-2008-055), it was noted that ‘poor maintenance procedures can lead to a range of errors including memory lapses, technical misunderstandings, and rule violations’.

Certification for a task after an extended period of time, in which multiple similar tasks were performed, can result in the misattribution of the source of memory at the time of certification. Misattribution of the source of a memory occurs when an individual recalls an item or fact from a past experience, but attributes it to an incorrect source of experience (Schacter, 1999). In the case of aviation maintenance, certifying for an inspection on aircraft A, when in fact it was performed on aircraft B, would be an example of possible source misattribution.

Closely related to source misattribution is the phenomena of suggestibility. The difference is that suggestibility includes an overt suggestion (Schacter, 1999). Presenting maintenance staff with a work-pack of recorded tasks for certification may introduce the suggestion of work completed, particularly if this is associated with the knowledge of a serviceable assessment from an operational check. This could result in staff certifying for tasks because they are listed on the work-pack for certification, rather than because they remember performing them.

Source misattribution and suggestibility are examples of retrospective memory errors at the time a certification is made. However, maintenance documentation is also important for prospective memory, which is remembering to complete a task in the future. According to Dismukes and Nowinski (2007), prospective memory is distinguished by three features: (1) an intention to perform an action at some later time when circumstances permit; (2) a delay between forming and executing the intention, typically filled with activities not directly related to the deferred action; and (3) the absence of an explicit prompt indicating that it is time to retrieve the intention from memory.

If an inspection of a system identified a requirement for re-work, and the re-work was completed at a time that the inspector was not available to re-inspect the work, then an omission to re-inspect would be an example of a possible prospective memory error. In this case, recording the disturbance (re-work) in the work-pack would provide a prompt to all relevant staff members that an independent inspection is required before the aircraft can be released from maintenance.

__________

  1. The flexible couplings in the R22 drive train accommodate differences in drive shaft axial alignment during helicopter operation. They are constructed by bolting a single, four-armed, thin stainless plate between the main rotor gearbox yoke and the drive shaft yoke.
  2. Coning of main rotor blades: the upwards movement of the main rotor blades while they are rotating. This is usually in response to an increase in aerodynamic force as a result of a control input from the pilot. It is more pronounced at high weights and/or low main rotor speed.
  3. Two elastomeric stops are fitted at the top of the main rotor mast to protect the mast from direct contact with the main rotor blades. Excessive teetering of the main rotor blades in-flight will result in the main rotor blades striking the teeter stops.
  4. Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.
  5. The swashplate consists of two main parts: a stationary swashplate and a rotating swashplate. The stationary (inner) swashplate is mounted on the main rotor mast and is connected to the cyclic and collective controls by the push-pull tubes. It is able to tilt in all directions and move vertically. The rotating (outer) swashplate is mounted to the stationary swashplate by means of a bearing, which allows it to rotate with the mast. The swashplates move as one unit. The rotating swashplate is connected to the main rotor blade pitch horns by the pitch links.
  6. Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.
  7. The process of smoothing vibrations in the airframe, which are caused by the main rotor.
  8. In accordance with the Civil Aviation Regulations 1988, Section 42G, any assembly, adjustment, repair, modification or replacement of any part of the flight control system requires an inspection by the person who conducted the work and an independent inspection by another appropriate person.
  9. Maintenance release: an official document, issued by an authorised person as described in Regulations, which is required to be carried on an aircraft as an ongoing record of its time-in-service (TIS) and airworthiness status. Subject to conditions, a maintenance release is valid for a set period, nominally 100 hours TIS or 12 months from issue.
  10. Out-of-ground-effect: helicopters require less power to hover when in ‘ground effect’ then when out of ‘ground effect’ due to the cushioning effect created by the main rotor downwash striking the ground. The height of ‘ground effect’ is usually defined as more than one main rotor diameter above the surface.
  11. Dewpoint: the temperature at which water vapour in the air starts to condense as the air cools. It is used, among other things, to monitor the risk of aircraft carburettor icing or the likelihood of fog.
  12. QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean seal level.
  13. Aerodrome forecast (TAF): a statement of meteorological conditions expected for a specific period of time in the airspace within a radius of 5 NM (9 km) of the aerodrome reference point.
  14. Ceiling and visibility okay (CAVOK): visibility, cloud and present weather are better than prescribed conditions. For an aerodrome weather report, those conditions are visibility 10 km or more, no significant cloud below 5,000 ft, no cumulonimbus cloud and no other significant weather.
  15. The published GPS data accuracy was plus or minus 7.5 m (24.6 ft) in the vertical plane during stable flight. At the time of the accident there were eight satellites visible with a geometric dilution of precision (GDOP) = 2.38, a rating of ‘good’ (2–5 = good; 1–2 = excellent).
  16. The Garmin GPS uses a Kalman Filter smoothing algorithm, which is a form of predictive smoothing. Data points may be recorded as predictive points, or as predictive points combined with actual measurements. It also uses an adaptive algorithm (variable sampling rate), which reduces the rate of recording during stabilised flight, and increases the rate of recording as the rate of horizontal or vertical manoeuvring increases. The GPS is designed to assist in normal flight, not to accurately record abnormal (highly dynamic) flight manoeuvres, which may not appear on a track log.
  17. The height range for the towers was based on their reported construction height of 40–60 m (131–197 ft).
  18. Above mean sea level.
  19. Irbesartan was an oral medication used to relax the blood vessels in order to lower blood pressure and increase the supply of blood and oxygen to the heart. This was considered to be a moderate dose, as the maximum dose is 300 mg.
  20. Eccentric stenosis is the asymmetric narrowing of a coronary artery.
  21. A build-up of plaque in the inner lining of an artery causing it to narrow or become blocked.
  22. The clinical forensic medicine unit reported that there could be several reasons why Irbesartan was not detected. The drug is broken down by the body for excretion with a rate dependent on individual differences. In addition, the level present in the body may have been below the cut-off value for testing and there may have been some post-mortem redistribution of the drug. Therefore, the level in death may not have been the level in life.
  23. The spindle tusk is part of the main rotor blade spindle, which contacts the droop stops attached to the main rotor shaft to minimise teetering when the blades are not rotating or turning at low speed.
  24. Refer to AO-2016-156: In-flight break-up involving Robinson R44, VH-ZNZ, 41 km NW Mossman, Queensland, 18 November 2016. Wreckage and impact information: Tailcone and tail rotor system.
  25. The term fastener refers to an assembly of bolt, washer(s) and nut(s).
  26. A self-locking nut is a nut that resists loosening under vibrations and torque.
  27. The bolt was found by a support person, working alongside the next-of-kin on 16 May 2018, as they were sieving through earth excavated from the site where the wreckage was buried. The bolt was photographed by the next-of-kin and images sent to the ATSB that same day. The bolt was received by the ATSB on 24 May 2018.
  28. The verification process included physical examination of the smaller assemblies by the ATSB, and photographic review of the larger assemblies, which revealed the presence of the fasteners as a result of the fire damage.
  29. Cadmium plating is a surface finish provided for corrosion resistance.
  30. Refer to section titled REF _Ref38333272 \h \* MERGEFORMAT Cloncurry Air Maintenance for the composition of the CAM workforce.
  31. Torque striping is the application of a thin lacquer to a bolt/nut to indicate it has been torqued to the correct value and provide a visual indication of any movement of the bolt/nut, which indicates a loss of torque.
  32. The chief engineer had completed the Robinson factory-sponsored maintenance course in 2009.
  33. This was not a maintenance controller, which is a CASA approved position for class A aircraft operations, but had similar responsibilities.
  34. The two observations were for control of parts and documents.
  35. A Palnut® is a secondary locking mechanism fitted to critical fasteners in most areas on the helicopter.
  36. Service letters SL-58, SL-38 and SL-01 preceded service letters SL-64, SL-50 and SL-09.
  37. Also refer to Civil Aviation Safety Authority Airworthiness Bulletin: 14-002, Cracked MS 21042 / NAS 1291 – Series Nuts – Hydrogen Embrittlement; and Transport Canada Civil Aviation Safety Alert 2013-04: Defective Standard Aircraft Hardware – Self-Locking Nuts – MS21042 and NAS11291.
  38. In August 2018, Textron published an information letter to owners and operators of Bell helicopters to inform them of the supersession of MS21042 and NAS1291 series nuts in response to reports of cracking from hydrogen embrittlement.
  39. For example, R44 Service Bulletin SB-88: Landing Gear Attach Nuts, required the replacement of NAS1291-7 nuts with D210-7 within 100 flight hours or by 28 February 2015.
  40. Previous work during the conduct of the ATSB investigation involving R44 helicopter VH-HFH (AO-2011-016) found that a MS21042Lseries self-locking nut could be reused up to 15 times without compromising the friction torque.
  41. AAR-13/01: Loss of Control Sundance Helicopters, Inc. Eurocopter AS350-B2, N37SH, Near Las Vegas, Nevada, December 7, 2011.

Safety analysis

Introduction

On the morning of 2 August 2017, the pilot of a Robinson R22 Betta II helicopter, registered VH‑HGU and operated by Cloncurry Mustering Company (CMC), departed Cloncurry Airport, Queensland on ferry flight in preparation for aerial mustering operations at various stations. About 3 minutes after take-off, the pilot experienced a loss of control and the helicopter broke-up in-flight. The helicopter collided with terrain about 7 km north-north-west of Cloncurry. The pilot, who was the only occupant, was fatally injured and the helicopter was destroyed. The accident flight was the first commercial flight of the helicopter after completing its second 2,200-hour overhaul.

While the pilot’s post-mortem examination identified coronary atherosclerosis, there was no evidence of a heart attack or stroke. Although it was noted that any conclusions could not be based on the examination alone. Despite this, the witnesses who encountered the pilot on the morning of the accident reported the pilot’s demeanour as normal. Further, a review of the GPS data did not find any indication of the pilot operating the helicopter erratically or attempting a descent to land. Therefore, it was unlikely that the pilot had experienced a medical event during the flight.

This analysis will discuss the likely reasons for the accident, the maintenance human factors issues of tracking tasks and workload, and organisational factors related to the quality assurance of the maintenance practices.

Loss of control and in-flight break-up

The condition of the tail rotor driveshaft indicated the tailcone was severed under normal engine power and rotor speed conditions. During a photographic review of the wreckage evidence, the ATSB noted the rear fastener for the cyclic assembly horizontal push-pull tube, which connected it to the bellcrank, was missing. All other bellcrank fasteners were in situ, and correctly assembled. The bellcrank and a bolt, believed to be from the missing fastener, were then recovered from the wreckage for examination.

The heat damage to the bolt, and lack of cadmium residue surrounding the bellcrank bolt hole, indicated the fastener was not fitted during the fire. In addition, the deformation of the bellcrank plates at the location of the missing fastener indicated the fastener was not fitted when the yoke and bellcrank were bent. Further, there was no damage to the bolt or bellcrank bolt holes to indicate the bolt was forcibly removed during the accident sequence. Therefore, it was concluded the bolt had separated from the bellcrank before impact. The absence of the fastener would have resulted in a disconnection of the longitudinal cyclic control. This in turn would have allowed the main rotor disc to tilt aft beyond the normal operating limits (rigging limits), striking the tailcone. Therefore, the severed tailcone was consistent with the separation of the longitudinal cyclic control in forward flight conditions.

The separation of the longitudinal cyclic control would result in the pilot losing pitch control of the main rotor disc. It was very likely that this occurred with little or no warning to the pilot, as there was no indication in the GPS data of an attempted landing. In addition to the loss of pitch control, the severed tail rotor driveshaft would have resulted in the pilot losing directional control. The impact damage and lack of ground witness marks from the main rotor blades, indicated that the helicopter broke-up in-flight.

Therefore, the loss of cyclic control was considered unrecoverable and was consistent with the helicopter colliding with the ground with a very high deceleration after the tailcone was severed.

Separation of the bolt

On consideration as to why the bolt had separated from the cyclic control bellcrank assembly, the ATSB had considered that the self-locking nut failed due to (1) over-torqueing, (2) fatigue cracking, (3) hydrogen embrittlement, (4) loosening, or (5) it was either not installed or was inadequately torqued. The most likely scenario was that the self-locking nut was either not reinstalled or was inadequately torqued.

Over-torqueing

The recovered bolt did not exhibit any damage (elongation) to the grip or threads to indicate it was exposed to excessive torque. Therefore, failure of the nut from over-torqueing was considered very unlikely.

Fatigue cracking

For the bellcrank, the design of the assembled joint is such that loads experienced by the fastener are predominantly a combination of tension within the bolt from axial preload of the joint as the nut is torqued to specification, shear loading of the bolt from operation of the cyclic, and high and low frequency dynamic loading from the rotor system, engine and other rotating components. In each case, the nut is under compression, rather than tension, predicating the likelihood of a nut failure by fatigue to be unlikely.

Hydrogen embrittlement

There have been several previous instances of self-locking nuts found cracked due to hydrogen embrittlement. In 2014, Robinson Helicopter Company released a service letter, which introduced the replacement by attrition of existing MS21042L-series and NAS1291-series nuts with D210‑series corrosion‑resistant nuts. However, in this case the evidence did not support hydrogen embrittlement as a failure mechanism of the missing nut due to the following:

  • The known batches of affected nuts were Airfasco, and the markings on the nuts installed on VH-HGU were not consistent with this manufacturer.
  • VH-HGU had been manufactured in 2008, prior to the manufacture of the affected batches of nuts in 2009 and 2010.
  • The nuts fitted to the bellcrank of VH-HGU had been in service for many years. Delayed hydrogen embrittlement generally occurs in the order of days and weeks, not years. In this time, the maintenance schedule meant there were many opportunities where the nuts would have been visible for inspection.
  • None of the remaining nuts on the bellcrank, or from the same manufacturer in other locations, exhibited any evidence of cracking associated with hydrogen embrittlement.

Therefore, failure of the self-locking nut from hydrogen embrittlement was considered very unlikely.

Loosening

While the repeated re-use of a self-locking nut could result in degradation and loss of its self‑locking capability, Cloncurry Air Maintenance (CAM) staff were aware of the limitation on their re-use, specifically that they could not be re-used if they had lost their friction torque. Previous work by the ATSB found that a MS21042L-series self-locking nut could be re-used up to 15 times without compromising the friction torque. The cyclic control is not disassembled during the 100‑hour inspection as the non-destructive inspection of parts is only performed at the 2,200-hour overhaul. If the bellcrank was disassembled at each 2,200-hour overhaul, then the nut would only have been re-used twice since production. So while it is possible that the nut had been re-used during the service life of the helicopter, separation of the bolt from the bellcrank from loosening of the nut as a result of a loss of torque in-service was considered unlikely.

Not installed or inadequately torqued

The bolt and bellcrank were found at the accident site and neither exhibited any physical evidence to indicate the fastener may have been predisposed to premature failure. The evidence indicated that the bolt was not installed in the bellcrank at the time of impact, which was about 3 minutes after take-off. It was therefore likely that the self-locking nut was either not installed, or that it was inadequately torqued, at the time of take-off. As it is not possible that there could have been ongoing operation of the helicopter with the nut not attached to the fastener, the most likely reason that the nut was either not installed or inadequately torqued on the accident flight, was due to the maintenance activities that were conducted during the previous 2,200-hour overhaul, completed 2 days prior to the accident.

The maintenance personnel could not recall the details of their work performed on the helicopter. However, they indicated that the bellcrank fasteners would not normally be disturbed when removing the cyclic assembly. Further, although there was no maintenance recorded to indicate that the fastener was disturbed during the overhaul, there were several reasons why the fastener may have been disturbed.

The possible reasons for disturbance of the fastener included inadvertent disassembly to separate the horizontal push-pull tube from the bellcrank, disassembly to measure play in the rod-end with a dial test indicator, or disassembly to adjust the length of the horizontal push-pull tube during the flight control rigging process. There were no records of any of these disturbances in the work‑pack. However, the ATSB noted that disturbances of the flight controls were not recorded in the work-pack, except for the standard overhaul requirements and for the replacement of parts.

The work-pack recorded several certifications for inspections. These inspections would have provided maintenance personnel with the opportunity to observe the bellcrank assembly. It could not be determined why none of these inspections detected an anomaly with the bellcrank fastener.

However, it was noted that the organisation’s maintenance practices relied significantly on human memory. The chief engineer and the head engineer both reported that after they conducted their inspections, they would provide a list of corrective actions. As these defects and corrective actions were not being tracked in the work-pack, and the maintenance staff were carrying a significant workload in the month leading up to the accident, their practices were considered to be conducive to a memory-related error event. These factors are discussed further in the following sections.

Maintenance practices

The 2,200-hour overhaul was the largest scope of maintenance activity for an R22 helicopter. It involved the disassembly of the helicopter, inspections and replacement of a significant number of parts with new or overhauled parts, and reassembly of the helicopter. A ground check and run up is required before the disassembly to capture any additional work for the overhaul. A 100-hour inspection, ground check, run up, track and balance, flight check, and weight and balance are conducted after reassembly and before return to service.

In order to track the progress of work, the CAM Maintenance Procedures Manual (MPM) required all tasks to be progressively certified. That is, certified at the time each item of work was completed. For VH-HGU, the aircraft worksheets were all certified at the end of the overhaul period, on 31 July 2017. Additional disturbances of the flight controls for adjustments and inspections were not recorded. Therefore, without recording all tasks and practicing progressive certification, the work‑pack was not an accurate record of the condition of the helicopter while under maintenance, or of all the work performed on completion of the overhaul.

In addition to the normal certification, any disturbance of the flight controls required an independent inspection. This required the inspector to verify that the work was carried out in accordance with the approved maintenance data and check that the system functioned correctly. The certification for independent inspections was not dated, but considered likely to be 31 July 2017 as it was the last entry in the aircraft worksheets. If it was on this date, then the helicopter was operated for the track and balance, autorotation RPM check and local area flight, without certification for independent inspections. As the disturbances of the flight controls for adjustments were not recorded in the work-pack, the integrity of the independent inspection process was reliant on informal methods of communicating additional work requirements and reporting their completion for re-inspection.

The work-pack included the 100-hour inspection, for which CAM had introduced an abbreviated checklist where a single certification could apply up to 30 separate inspection items. There were no dates recorded for the certifications, but they likely occurred on 31 July 2017. This suggested the checklist was not used to track the 100-hour inspection tasks and manage any interruptions during the process.

When the ATSB reviewed work-packs from other maintenance activities in 2015 and 2016, and the observations made by the Civil Aviation Safety Authority (CASA) audit of 2018, it was apparent that the maintenance documentation practices for VH‑HGU were not an isolated case. The evidence suggested a systemic issue within CAM of not using the maintenance documentation to track the condition of helicopters while under maintenance and to record all maintenance activities.

The use of work-packs at CAM was consistent with the culture of recording and certifying for maintenance for oversight purposes, rather than for quality control in accordance with their MPM. Circumventing the quality control procedures may render them ineffective as a means for ensuring all tasks have been completed correctly.

Extended periods of time between performing and certifying for tasks increased the likelihood of an individual’s memory being subject to source misattribution or suggestibility, or combination of both, when the certification was made. Omissions to record and capture all flight control disturbances in the work-pack increased the likelihood of a prospective memory error during the overhaul period. Therefore, the maintenance practices at CAM exposed the organisation to an increased risk of memory‑related errors and the omission of tasks.

Organisational structure and workload

In the period 2013 to 2017, the CAM workforce structure changed from a majority of licenced aircraft maintenance engineers to three apprentices with one aircraft maintenance engineer and two licenced aircraft maintenance engineers. CAM undertook maintenance for CMC helicopters as one part of its operation, as well as maintenance of helicopters from external operators as another part. With one licenced aircraft maintenance engineer and apprentice assigned to the external helicopters, and one apprentice attending trade school in the period leading up to the accident, there were effectively three members of staff for the CMC helicopters (chief engineer, aircraft maintenance engineer and a fourth-year apprentice).

Further, the structure of the workforce required the chief engineer to assume responsibility for the planning, supervision and coordination of maintenance for the CMC jobs. When the ATSB attempted to obtain details about the maintenance of the cyclic assembly on VH-HGU, the staff consistently reported that they could not recall specific details, and that it was a busy period with the overhaul constantly interrupted for 100-hour inspections. The month leading up to the accident included 20 100-hour inspections on CMC helicopters, which was consistent with the staff reports of it being a busy period.

The ATSB used a labour-hour plan to review the CAM staffing levels over this period and established that 100-hour inspections should have taken about 480 labour-hours. This equated to a requirement for three full-time qualified staff members, in addition to what was required to progress the overhaul for VH-HGU.

The volume of work and turn-around times were consistent with the peak mustering season and the staff reports of regular interruptions to the overhaul for other jobs. If the workforce structure does not change as the production requirements increase, it is likely that junior personnel will be allocated more responsibilities. This may occur concurrently with less supervision if the supervisor’s workload must also increase to deliver the production goals.

Therefore, the volume of work and interruptions to the overhaul in the month of July 2017, combined with the low levels of staff experience and qualifications, and maintenance practices, increased the risk of a maintenance error event. In addition, the intensity of the work likely reduced the chief engineer’s capacity to effectively supervise all the activities related to the CMC helicopters.

Internal independence

The CMC-CAM managing director was the CASA approved Head of Aircraft Airworthiness and Maintenance Control. This position is intended to provide an interface with maintenance organisations for the planning and preparation of maintenance activities, and an independent check of the completion of those activities.

The managing director, who had a pilot background, had delegated the Head of Aircraft Airworthiness and Maintenance Control responsibilities to the position of maintenance coordinator, which was filled by the chief engineer at the time of the accident. This decision resulted in the same individual holding the two key positions of airworthiness and maintenance management within CMC and CAM. As a result of this structure, the chief engineer had a considerable number of responsibilities and there was no independent assurance of maintenance quality from the Air Operator Certificate holder. In addition, there was no requirement for CAM to have a quality manager to routinely monitor, measure and evaluate the organisation’s performance, and advise the managing director and chief engineer of the results.

In the absence of an independent maintenance coordinator or quality manager, the organisation was operating with very few checks and balances. In addition, the ATSB noted that all maintenance staff, including the chief engineer, were trained through their apprenticeships at CAM. The home‑grown workforce, combined with no permanent internal independent oversight, limited CAM’s exposure to alternative maintenance practices and continuous improvement.

Audit oversight

In the absence of a quality manager for CAM, the role of internal audit was managed by contracting an external auditor. The ATSB reviewed the two internal audits performed in 2015 and 2016, and noted there were no findings, no requests for corrective action and no suggestions for improvements. Upon review of the work-pack sampled in the 2016 audit, the ATSB noted there was no evidence of progressive certification, an abbreviated 100-hour inspection checklist was used, and a single certification was made for the entire 100‑hour inspection on the airframe, ground check and run up.

The observations of the sampled work-pack suggested it was not used to track the progress of maintenance, which presented the risk of the omission of inspections during periods of interruptions. In contrast, the Robinson Helicopter Company maintenance manual checklist for the 100-hour inspection provided points of certification for each item. Chapter 6 of the CAM MPM included the requirements to conduct maintenance in accordance with approved data and to progressively certify for each item as it is completed. Use of the Robinson Helicopter Company checklist would have provided the auditor with evidence that approved data was used and current, and that it facilitated progressive certification, thereby demonstrating that requirements were being met.

Similarly, in 2015, CASA performed their last system-based audit of CAM prior to the accident. The auditor sampled three work-packs, which included a 2,200-hour overhaul for an R22, with no issues identified. The reported criteria for the sampling was Chapter 6 of the CAM MPM. The ATSB’s review of that work-pack found that it did not capture all the requirements of the overhaul procedure or progressive certification. Therefore, it did not conform to Chapter 6 of the MPM. However, a post-accident audit conducted by CASA identified a number of findings similar to those observed by the ATSB.

From the ATSB’s review of the sampled work-packs, it was noted that the maintenance practices employed by CAM during the overhaul of VH-HGU were present before the helicopter was acquired by CMC in February 2017 and entered overhaul. These practices were visible to auditors engaged in internal and external audits of CAM and indicated that the work-packs were not being used for progressively recording and tracking tasks. Consequently, the audits were missed opportunities to identify and recommend improvements to the practices employed by CAM staff, which limited their benefit to CAM as a quality assurance tool.

Re-use of self-locking nuts

In the course of interviewing personnel employed by CAM, the ATSB noted a low level of awareness of the need to replace MS21042L/NAS1291-series nuts with the D210-series nuts when critical fasteners were reassembled. In accordance with the R22 maintenance manual, critical fasteners include a self-locking nut in their assembly. It is a standard practice within sectors of the aviation industry to re-use self-locking nuts provided the nut cannot be turned onto the bolt thread by hand and the published torque value for the fastener is achieved.

In December 2018, the ATSB received the accident helicopter’s jackshaft, which had the fasteners attached. The jackshaft was one of a number of parts within the flight control system that was disassembled and sent for non-destructive inspection during the 2,200-hour overhaul. In late January 2019, the ATSB completed semi-quantitative chemical analysis of the nuts fitted to the jackshaft and found they were consistent with a carbon/alloy steel, and therefore not consistent with D210-series stainless steel corrosion-resistant nuts.

At the time of the reassembly of the accident helicopter, the current R22 Illustrated Parts Catalog detailed the part number D210-4 for the nuts fitted to the jackshaft, and RHC confirmed there was no alternate part number to the D210-series nuts. Therefore, the ATSB concluded that the industry practice of re-use of self‑locking nuts on Robinson helicopters may result in the omission to install D210-series nuts when critical fasteners are reassembled.

Findings

From the evidence available, the following findings are made with respect to the loss of control and in-flight break-up involving the Cloncurry Mustering Company Robinson R22 helicopter, registered VH-HGU, 7 km north-north-west of Cloncurry Airport, Queensland, on 2 August 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.

Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.

Contributing factors

  • About 3 minutes after take-off, a bolt separated from the cyclic control bellcrank, which resulted in an unrecoverable loss of control, in-flight break-up and collision with terrain.
  • The bolt separated from the bellcrank during flight, likely due to either the self-locking nut not being reinstalled or inadequate torque of the nut on completion of the 2,200-hour overhaul. The accident flight was the first commercial flight after the 2,200-hour overhaul.

Other factors that increased risk

  • Cloncurry Air Maintenance had adopted a number of practices, which included using abbreviated inspection checklists, not recording all flight control disturbances and not progressively certifying for every inspection item as the work was completed, which increased the risk of memory-related errors and the omission of tasks. [Safety Issue]
  • The number of helicopters for which maintenance was performed in the month leading up to the accident likely exceeded the workforce capability, given the staffing levels and qualifications. This likely reduced the capacity of the chief engineer to conduct oversight activities and increased the risk of a maintenance error not being captured.
  • Cloncurry Air Maintenance had limited internal independent oversight and increased reliance on audits for the evaluation of its quality performance. This was partly due to:
    • the absence of an independent maintenance coordinator or quality manager, and
    • all maintenance staff had worked almost exclusively for Cloncurry Air Maintenance, which limited the organisation's exposure to other maintenance practices.
  • The most recent contracted audit of Cloncurry Air Maintenance, performed as part of the organisation's quality activities, and the previous audit conducted by the Civil Aviation Safety Authority, did not provide any observations of error-conducive maintenance practices, although they were present at the time. These were missed opportunities to identify and recommend improvements to the tracking and certification of maintenance tasks.
  • During reassembly of the helicopter after the 2,200-hour overhaul, self-locking nuts, consistent with MS21042L-series nuts, were re-used on critical fasteners without replacing them with D210-series corrosion resistant nuts in accordance with the manufacturer's instructions for continued airworthiness. The D210-series nuts were introduced to reduce the risk of hydrogen embrittlement cracking from the MS21042L-series and NAS1291-series nuts.

Other findings

  • There was no recorded maintenance on the helicopter to indicate that the bellcrank fastener was removed, and it was not always necessary to disassemble it during the 2,200-hour overhaul. However, there were several reasons why it could have been disturbed. These included disturbance as part of the disassembly of the cyclic control assembly, disassembly to inspect the attached rod-end with a dial test indicator, or disassembly to adjust the length of the horizontal push-pull tube as part of the main rotor rigging process. However, based on the evidence available, the ATSB could not establish if any of these tasks were performed.
  • On completion of the helicopter's 2,200-hour overhaul, there were several certifications for inspection of the cyclic control assembly. The reason why these inspections did not detect an anomaly with the cyclic bellcrank fastener could not be determined.

Safety issues and actions

The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.

Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.

All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.

Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.

Maintenance practices

Safety issue number: AO-2017-078-SI-01

Safety issue description: Cloncurry Air Maintenance had adopted a number of practices, which included using abbreviated inspection checklists, not recording all flight control disturbances and not progressively certifying for every inspection item as the work was completed, which increased the risk of memory-related errors and the omission of tasks.

Additional safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence:

Australian Transport Safety Bureau

ATSB safety advisory notice to maintenance personnel for Robinson helicopters 

Safety Advisory Notice: AO-2017-078-SAN-001

In March 2019, the Australian Transport Safety Bureau issued a safety advisory notice advising all Australian maintenance personnel for Robinson helicopters to ensure that before re-using a self-locking nut, that the correct part number is fitted, and that the D210-series corrosion-resistant nuts are used for reassembly of critical fasteners in accordance with the Robinson Helicopter Company instructions for continued airworthiness.

Civil Aviation Safety Authority 

Airworthiness bulletin 67-005

On 5 June 2019, the Civil Aviation Safety Authority released airworthiness bulletin (AWB) 67-005 Issue 1: Robinson Helicopter Flight Controls – Duplicate Inspections [independent inspection]. The purpose of AWB 67-005 was to advise all operators and maintainers of the need to replace MS2104 hardware during removal or replacement of such hardware and the requirement to complete a duplicate inspection of each stage of maintenance on the primary flight controls.

On 20 June 2019, the Civil Aviation Safety Authority released AWB 67-005 Issue 2: Robinson Helicopter Flight Controls – Independent Inspections. Issue 2 highlighted the need for independent inspections to be conducted and ‘recorded consecutively with each adjustment made during rotor tracking and balancing’ activities. In addition to several recommendations, Issue 2 identified several human factor elements that could impact inspection performance, and highlighted the need for extra caution during post-maintenance flights in accordance with Robinson Helicopter Company safety notice SN-43:

…any work completed on the flight control system deserves special attention because a flight control disconnect is almost always catastrophic.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • Civil Aviation Safety Authority
  • Cloncurry Air Maintenance
  • Cloncurry Flinders Medical Centre
  • Cloncurry Mustering Company
  • Ergon Energy
  • Pilot’s next-of-kin
  • Queensland Department of Health
  • Queensland Police Service
  • Robinson Helicopter Company
  • United States National Transportation Safety Board.

References

Australian Transport Safety Bureau 2019, AO-2016-156: In-flight break-up involving Robinson R44, VH-ZNZ, 41 km NW Mossman, Queensland, 18 November 2016, ATSB, Canberra.

Australian Transport Safety Bureau 2014, AO-2011-135: Embrittled nut and related failures Robinson R22 Beta helicopter, VH-JNP, 22 km N of Saxby Downs, Queensland, 12 October 2011, ATSB, Canberra.

Australian Transport Safety Bureau 2012, AO-2011-016: Loss of control, Robinson Helicopter R44 Astro, VH-HFH, Cessnock Airport, New South Wales, 4 February 2011, ATSB, Canberra.

Australian Transport Safety Bureau 2008, AR-2008-055: An Overview of Human Factors in Aviation Maintenance, report prepared by A Hobbs, Canberra.

Dismukes, K and Nowinski, J 2007, ‘Prospective memory, concurrent task management, and pilot error’. In AF Kramer, DA Wiegmann and A Kirlik (Eds.), Series in human-technology interaction. Attention: From theory to practice (pp. 225–236), Oxford University Press.

National Aerospace Standard, NAS6603 thru 6620, Bolt, tension, hex head, close tolerance, alloy steel, long thread, reduced major dia., self-locking and non-locking, 160 KSI Ftu, Revision 8, June 12, 2009.

Schacter, LD 1999, ‘The seven sins of memory: Insights from psychology and cognitive neuroscience’, American Psychologist, vol. 54, no. 3, pp. 182-203.

United States National Transportation Safety Board 2013, NTSB/AAR-13/01: Loss of Control, Sundance Helicopters, Inc. Eurocopter AS350-B2, N37SH, Near Las Vegas, Nevada, December 7, 2011, NTSB, Washington.

Wagtendonk, WJ 2011, Principles of helicopter flight, 2nd edn, Aviation Supplies & Academics Inc., Washington.

Submissions

Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the Civil Aviation Safety Authority, Cloncurry Air Maintenance and Cloncurry Mustering Company personnel, pilot’s next-of-kin, pilot’s designated aviation medical examiner, Queensland Department of Health, Queensland Northern Coroner, Robinson Helicopter Company and the United States National Transportation Safety Board.

Submissions were received from the Civil Aviation Safety Authority, Cloncurry Air Maintenance and Cloncurry Mustering Company, pilot’s next-of-kin, pilot’s designated aviation medical examiner, Queensland Northern Coroner and the Robinson Helicopter Company. The submissions were reviewed and where considered appropriate, the text of the draft report was amended accordingly.

Appendices

Appendix A – Materials examination report

Introduction

Following a review of the site images for the wreckage of VH-HGU and impact information, a critical fastener from the cyclic control system was identified to be missing. The cyclic is one of the primary controls that a pilot must use during flight. It allows flight to be controlled in any direction of travel by tilting the main rotor disc. The cyclic stick within the R22 cabin was coupled to a non‑rotating swashplate by a mechanical linkage comprising push-pull tubes, pivots, a bellcrank and its associated fasteners (e.g. bolts and nuts, rod ends, spacers and washers). The underfloor bellcrank provided the linkage between the horizontal and vertical push‑pull tubes. It transmitted horizontal push-pull tube movement to vertical movement that tilted the swashplate, producing an associated tilting of the main rotor disc.

The missing fastener was normally installed in the bellcrank, connecting through the rod end of the horizontal push-pull tube (Figure A1). Due to the criticality of this fastener in relation to the operation of the cyclic control and its absence predicating an in-flight loss of control, several items from the wreckage were recovered from the accident site. The retained items were examined in closer detail at the ATSB’s technical facilities in Canberra. They included:

  • bellcrank (part number A958-1) and associated componentry
  • recovered pieces of metallic debris
  • jackshaft (part number A337-1) and associated componentry
  • a single NAS6604-15 bolt
  • additional loose nuts and washers
  • forward support assembly (part number A014-6).

Figure A1: View looking upwards of an exemplar R22 control system, showing the bellcrank and location of the missing fastener
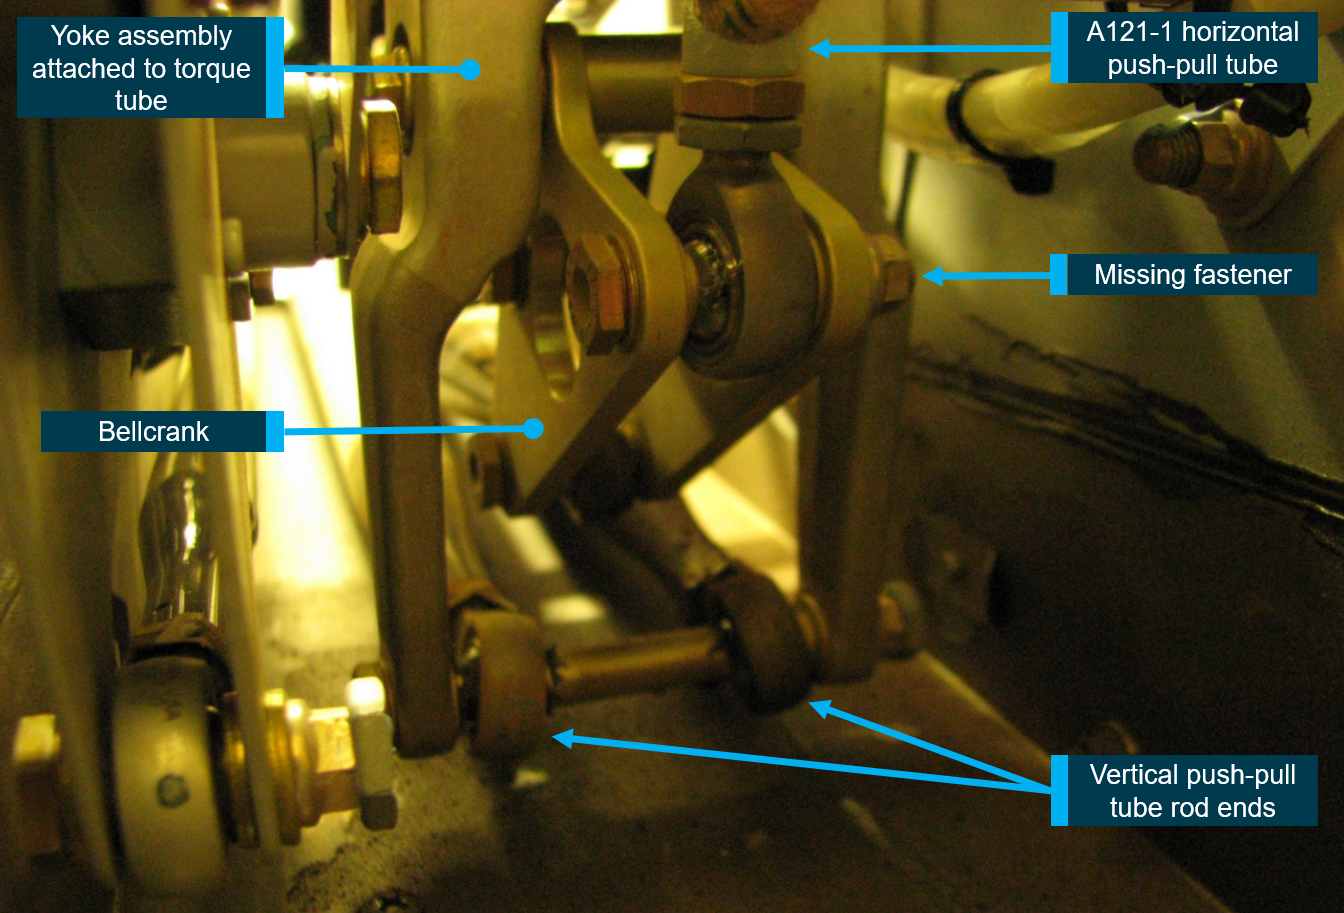
Figure A1: View looking upwards of an exemplar R22 control system, showing the bellcrank and location of the missing fastener.
Source: ATSB

Source: ATSB

Scope

The scope of the examination was to analyse the bellcrank, yoke, and related components to determine how the fastener came to be missing, and to examine the pieces of metallic debris to determine if any additional components could be recovered. The jackshaft shared the same fastener type as the bellcrank assembly and was examined for comparative purposes. Additionally, the forward support assembly was used to verify the presence and security of NAS6604-15 bolts.

Examination

Bellcrank fasteners

The missing bellcrank fastener was an assembly of components comprised of the following (Figure A2):

  • NAS6604-15 bolt
  • NAS1149F0432P washer
  • A115-1 spacer
  • B332-441 lockwasher
  • D210-4 nut
  • rod-end.

Figure A2: Modified image from the R22 Illustrated Parts Catalog showing missing fastener assembly components and location
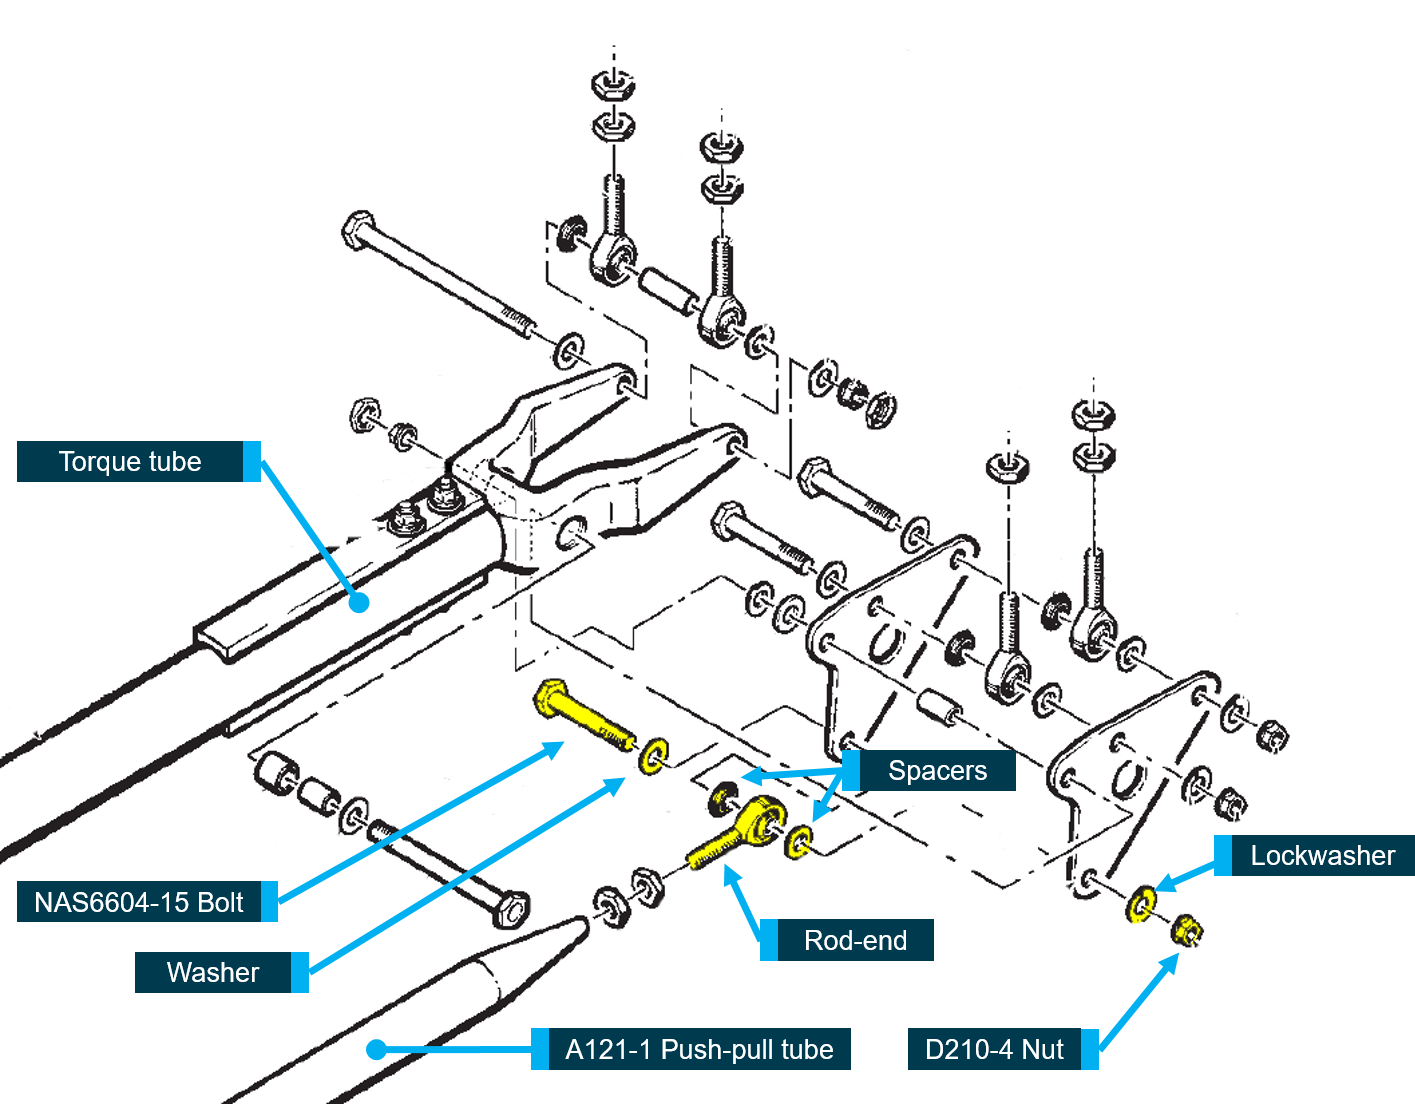
Figure A2: Modified image from the R22 Illustrated Parts Catalog showing missing fastener assembly components and location .
Source: Robinson Helicopter Company, annotated by the ATSB

Source: Robinson Helicopter Company, annotated by the ATSB

Specified bolt

The current Robinson Helicopter Company (RHC) R22 Illustrated Parts Catalog (IPC) showed that the horizontal and vertical push-pull tubes from the cyclic control assembly were required to be attached to the bellcrank with a National Aerospace Standard (NAS) 6604-15 bolt[43] and D210-4 nut. The NAS specification listed the material type as alloy steel, grade 4140, 4340, or 8740. Table A1 provides the bolt dimensions from that specification.

Table A1: NAS6604-15 bolt specifications

BoltThread
UNJF-3A
Width
(flats) (in)
Shank diameter
(in)
Thread length
(in)
Grip length
(in)
Length
(in)
Height (head)
(in)
NAS6604-15
bolt
0.2500-280.429-
0.439
0.2485-
0.2495
0.4250.9381.3630.125

Specified nut

Prior to 2014, the specified nut was an MS21042L-series or NAS1291-series. However, RHC issued a R22 service letter SL-64, D210 Corrosion-Resistant (CRES) nuts, on 13 October 2014, which addressed potential cracking of MS21042L-series nuts.

The D210-series CRES nuts, which supersede MS21042L-series and NAS1291-series nuts, are not susceptible to cracking. The service letter directed that when performing maintenance that involved disassembly of a critical fastener (joints with a secondary lock), the fastener should be reassembled using a D210-series nut. The IPC was updated in February 2017 to reflect these changes. Table A2 provides the dimensions of the nuts.

Table A2: Bellcrank nut specifications

NutHeight
(in)
Width
(flats) (in)
Material
MS21042-L4 / NAS12910.204-0.2190.304-0.316Alloy steel, grade 1035, 1042, 1050, 4027, 4037, 8630 or 8740. Cadmium plated
D210 corrosion-resistant (CRES) nut0.205-0.2190.304-0.316Stainless steel 660
Recovered bellcrank

The recovered bellcrank remained attached to the torque tube yoke assembly, which had fractured at the termination of the attached stiffening brackets. The submitted assembly exhibited significant damage as a result of mechanical and heat effects. All remaining rod ends, including those attached to the vertical push-pull tubes and collective fork assembly, had fractured in overstress (Figure A3).

Figure A3: Side view of the bellcrank as received, location of missing fastener circled
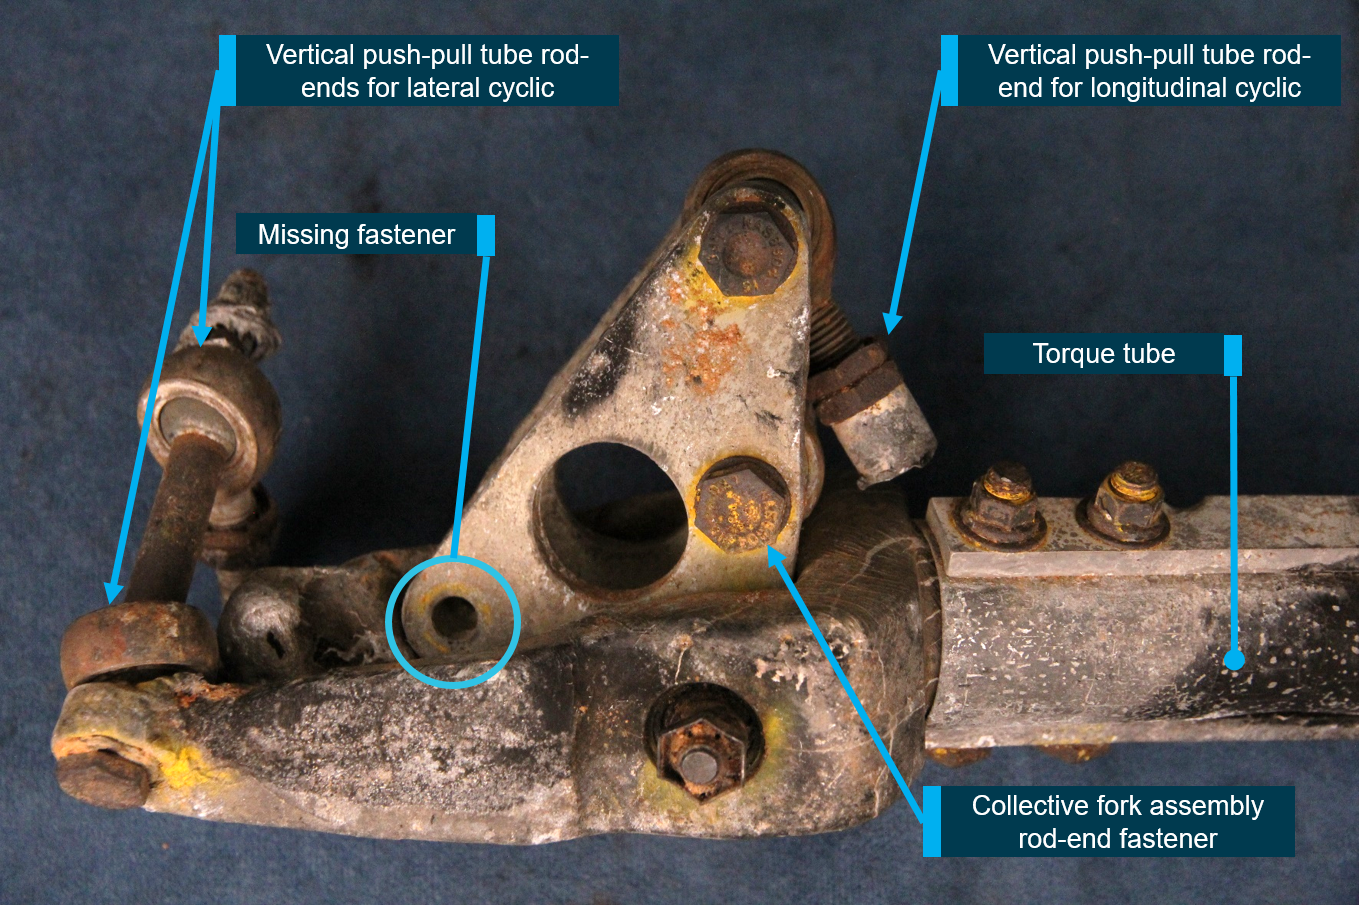
Figure A3: Side view of the bellcrank as received, location of missing fastener circled.
Source: ATSB

Source: ATSB

The torque tube yoke assembly had separated from the bolt for the lateral cyclic vertical push-pull tube rod end on the left side, and was distorted from a combination of mechanical impact and heat. The left side of the yoke assembly exhibited significant distortion, and had been plastically deformed inward, towards the right side. The left bellcrank plate had been distorted in a similar way, causing the two plates to come together at the location of the missing fastener. The yoke assembly also exhibited heat damage in this area, with the left side moulding around the bellcrank plate (Figure A4).

Figure A4: Side view of the bellcrank as received showing deformation of yoke and plate

Figure 9: Bellcrank showing deformation observed on the torque tube yoke assembly and bellcrank plates.
Source: ATSB

Source: ATSB

Following initial visual examination and photography, the bellcrank was removed from the torque tube yoke assembly for further examination. The bellcrank exhibited distortion from a combination of mechanical stress and heat effects. The two plates of the bellcrank had been deformed along the length between the vertical push-pull tube and torque tube attachment ends (Figure A5). Where the fasteners remained in position, the two plates had deformed in parallel. However, as above, where the fastener was missing, the two plates of the bellcrank had been pushed closer together.

Figure A5: Bellcrank following removal from the torque tube and showing parallel deformation of both plates
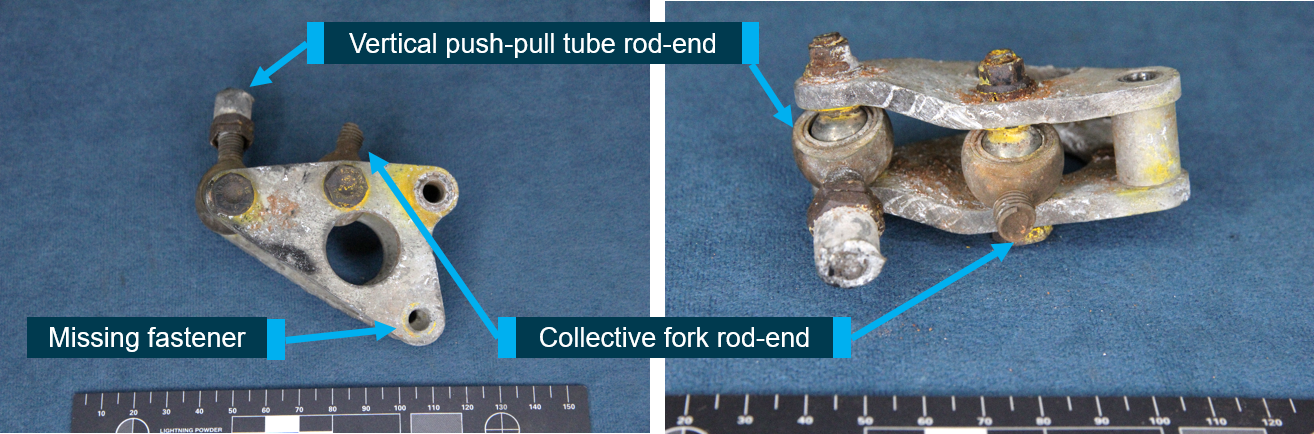
Figure A5: Bellcrank following removal from the torque tube and showing parallel deformation of both plates.
Source: ATSB

Source: ATSB

Closer examination of the bellcrank plates showed that a yellow residue had been deposited around the holes where the bolts had been in position. However, there was minimal residue around the hole where the fastener was missing (Figure A6). The manufacturer advised the residue was likely cadmium plating from components within the fastener assembly that had melted during the fire. They were also of the opinion that the minimal residue observed around the hole where the fastener was missing was likely from cadmium plating transfer from a previous installation. The presence of cadmium within the residue was confirmed by semi-quantitative chemical analysis using a scanning electron microscope (SEM) equipped with an Oxford energy dispersive x-ray spectrometer (EDS).

Figure A6: Bellcrank internal surfaces showing the cadmium plating residue

Figure 10: Bellcrank internal surfaces with yellow colouration.
Source: ATSB

Source: ATSB

There was no evidence of deformation or elongation of the bellcrank fastener hole to suggest that the nut and bolt had detached forcefully during the collision. The surface of the bellcrank in the region adjacent to the missing bolt, and the internal surface of the bolt hole, was rippled as a result of high temperatures associated with the fire. Minor damage in the form of scrapes and dents were observed in the region adjacent to the bolt hole of the missing fastener, coincident with where it had been in contact with the torque tube yoke assembly (Figure A7).

Figure A7: Comparison between the bolt hole where the fastener was missing (left) showing deformation due to heat and a bolt hole where a fastener remained in position (right)

Figure A7: Comparison between the bolt hole where the fastener was missing (left) showing deformation due to heat and a bolt hole where a fastener remained in position (right).
Source: ATSB

Source: ATSB

An exemplar bolt could not be inserted through the bellcrank bolt holes where the fastener was missing. This was due to a combination of misalignment of the two plates as a result of impact damage, and the heat damage observed on the internal surfaces of the holes.

Remaining bellcrank bolts

Markings on heads of the two remaining bolts from the bellcrank indicated they were a NAS6604‑15 bolt. The marking ‘LFC’ stamped on the bolt head identified the manufacturer (Figure A8). As per United States Department of Defence Handbook, MIL-HDBK-57G (IS) 16 October 2012, Listing of Fastener Manufacturer’s Identification Symbols, the manufacturer was likely to be: LFC Industries, Texas, USA.

Figure A8: Bolt head markings from one of the remaining bellcrank bolts
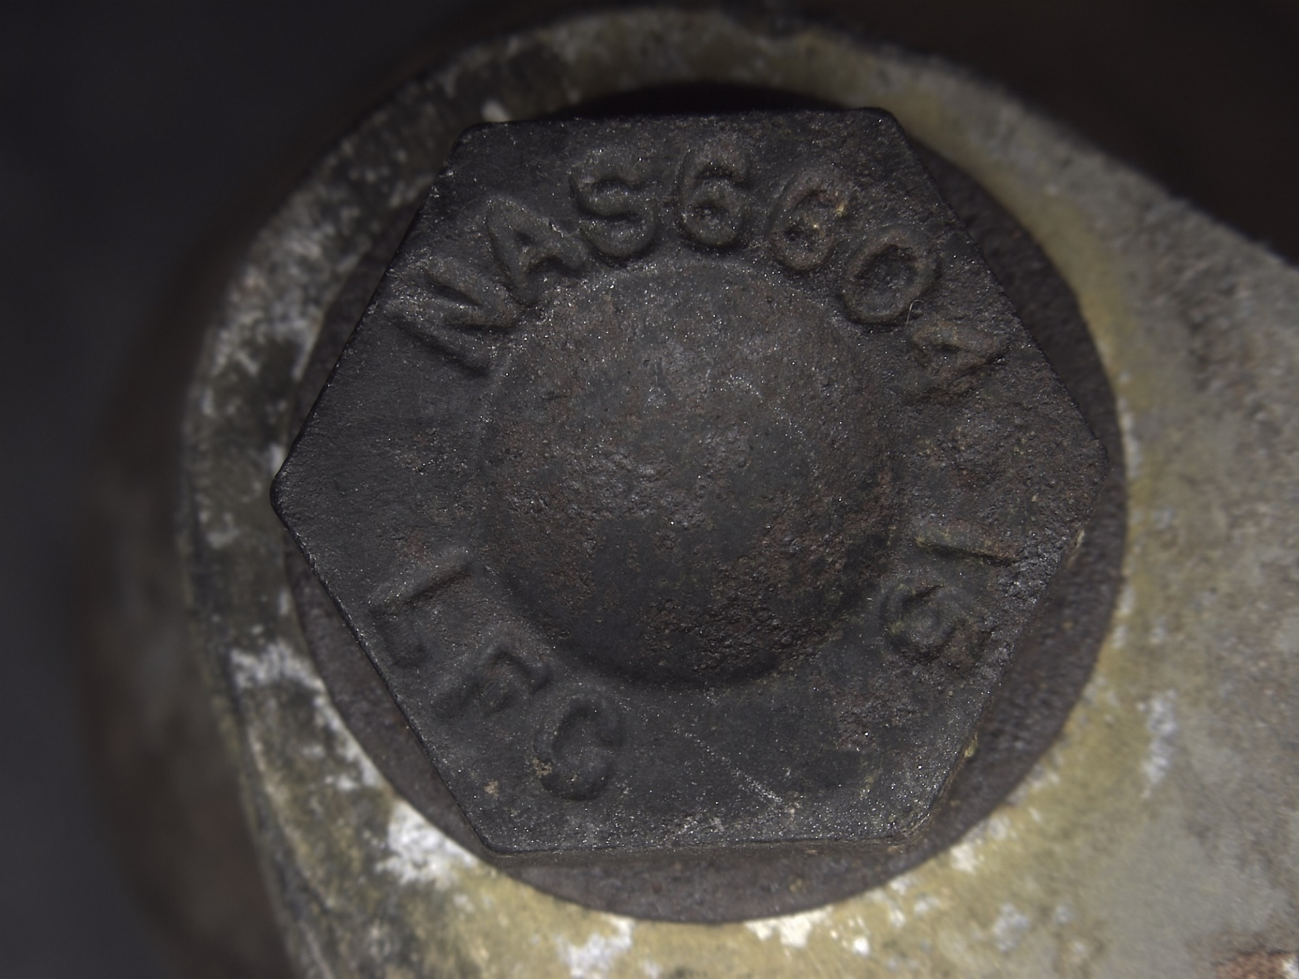
Figure A8: Bolt head markings from one of the remaining bellcrank bolts .

Source: ATSB

Remaining bellcrank nuts

The nuts of the two remaining fasteners were stamped with an ’R’ symbol on two of the hexagon flats on opposite sides. As per United States Department of Defence Handbook, MIL-HDBK-57E Listing of Fastener Manufacturer’s Identification Symbols, the nuts were most likely manufactured by Ronson Manufacturing Inc. (Figure A9). The two remaining nuts were in relatively good condition, with no evidence of any cracking or damage observed. The chemical analysis results, provided in Table A3, confirmed the nuts were manufactured using 4037 alloy steel. Measurements and chemical analysis confirmed that they were consistent with MS21042‑L4/NAS1291-series nuts.

Figure A9: Nut markings from one of the remaining fasteners (left) and relevant page from MIL-HDBK-57 showing manufacturers marks (right)
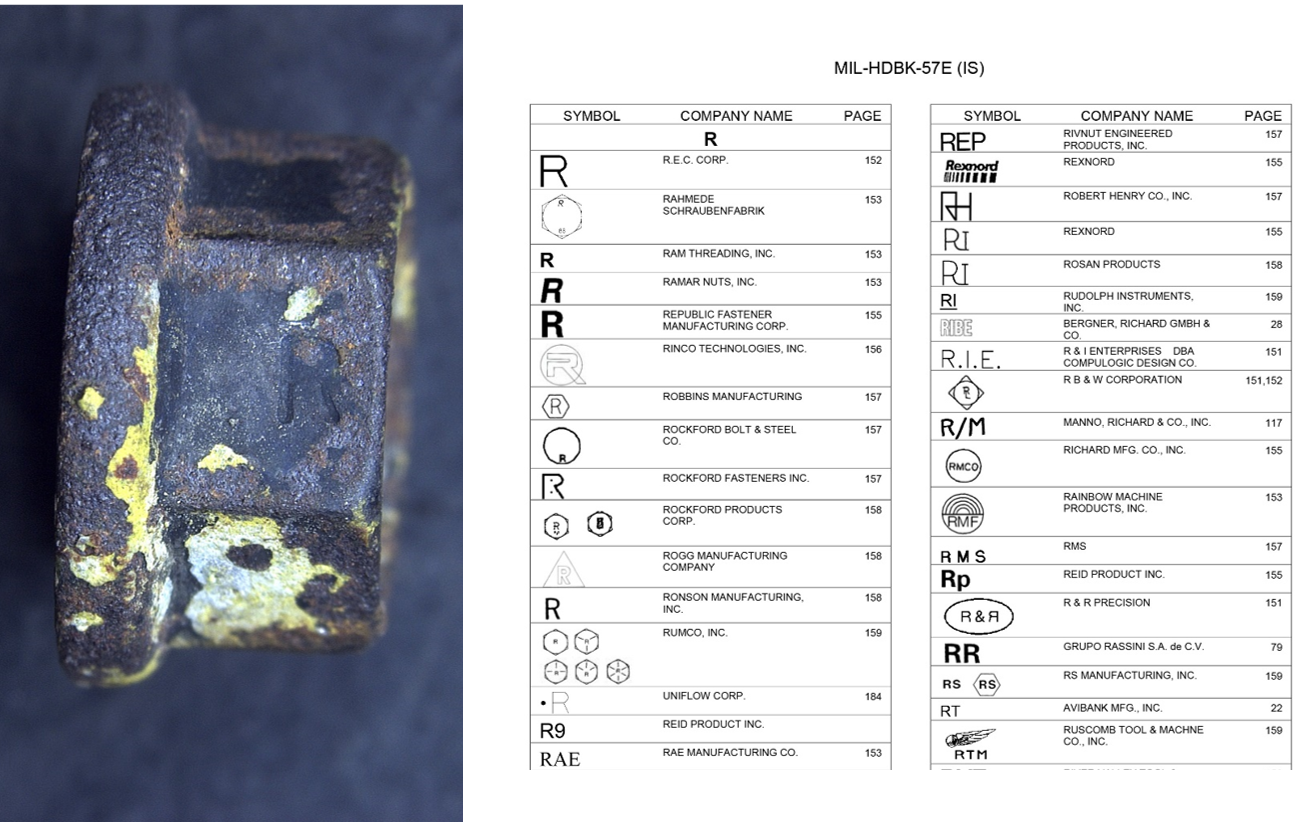
Figure A9: Nut markings from one of the remaining fasteners (left) and relevant page from MIL-HDBK-57 showing manufacturers marks (right).
Source: ATSB

Source: ATSB

Table A3: Chemical analysis results for a nut removed from the bellcrank

SpecificationFeCMnSiSPNiCrMoCuVAl
Bellcrank nutBal0.390.750.260.010.010.050.190.230.120.010.023
Alloy 4037
 
-0.35-0.400.70-0.900.15-0.350.040.35--0.20-0.30---

Units are weight %

Additional recovered bolt

The bolt found on 16 May 2018 by the pilot’s next-of-kin displayed the same markings as those that remained in position on the bellcrank (NAS6604-15 manufactured by LFC) (Figure A10). The surfaces of the bolt were severely heat affected, with areas of material loss and areas where additional material had adhered to the surface. Ultrasonic chemical cleaning of the bolt was unable to remove much of the adhered material. There was no damage observed to the head, shank or threads of the bolt. A dial indicator was used to check the bolt run-out, which confirmed it to be straight without significant distortion along the length.

Figure A10: NAS6604-15 bolt found 16 May 2018

Figure A10: NAS6604-15 bolt found 16 May 2018.
Source: ATSB

Source: ATSB

Closer examination of the bolt threads confirmed significant heat damage, and a small groove located on the second to third threads from the end of the bolt (Figure A11). Other than the small groove, the bolt threads did not show any other markings such as grooves, score marks or galling.[44] A similar marking was observed on the other bellcrank bolts. This indicated that a nut had been installed at some point on the examined bolt. The bolt was examined using a scanning electron microscope equipped with an Oxford energy dispersive x-ray spectrometer. No evidence of remnant cadmium plating was detected on the bolt surfaces.

Figure A11: Magnified image of the NAS6604-15 bolt found 16 May 2018 showing thread groove

Figure 12: Magnified image of the bolt found 16 May 2018 showing thread groove.
Source: ATSB

Source: ATSB

Radiography of metallic debris

Aluminium alloy portions of the helicopter had melted during the post-accident fire and then resolidified into blobs of metallic debris. The debris was gathered from the wreckage and submitted to the Australian National University for radiography[45] to determine the presence of entrapped hardware (e.g. nuts, bolts, washers) that may have been similar in size or shape to the components from the fastener assembly missing from the bellcrank.

While some samples did show evidence of steel componentry, including nuts and bolts, within the solidified metallic debris, nothing was identified that was similar in size or shape to a NAS6604-15 bolt, D210-4 nut, or MS21042-L4/NAS1291-series nuts. The fasteners identified were too long or short, threaded the entire length, were a complete assembly (nut was still attached), had a different shaped head or were attached to other componentry (Figure A12).

Figure A12: One of the metallic pieces recovered from the accident site and the corresponding radiograph that highlighted the presence of entrapped steel hardware

Figure A12: One of the metallic pieces recovered from the accident site and the corresponding radiograph that highlighted the presence of entrapped steel hardware.
Source: ATSB (left) and Australian National University (right)

Source: ATSB (left) and Australian National University (right)

Dissolution of metallic debris

Following the suspected recovery of the missing bolt from the bellcrank, an internal technical review of the radiography questioned if that technique was capable of resolving a small part, such as a D210-4 or MS21042-L nut. When taking into account potential for hydrogen embrittlement and cracking of the MS21042-L series nuts, it was considered that, if the nut had fractured into thirds, it may not have been visible on the radiographs. As such, the metal pieces were dissolved in a caustic soda (sodium hydroxide) solution. The resulting solution was sieved using a 352 mesh (minimum captured particle size of 1.5 mm) to recover the entrapped hardware.

A number of fasteners and other components were recovered following dissolution of the aluminium (Figure A13). The missing nut to the bellcrank fastener was not amongst the entrapped hardware. Neither a D210-4 nor MS21042-L series (whole or in part) nut was among the recovered items.

Figure A13: Recovered items following dissolution of the metallic debris

Figure A13: Recovered items following dissolution of the metallic debris.
Source: ATSB

Source: ATSB

Additional hardware

Additional hardware was received in June 2018 by the ATSB, which included:

  • additional fastener parts (four small bags of nuts and washers)
  • forward support assembly (part number A014-6) with two NAS6604-15 bolts.

The samples were examined to identify the fastener designations, verify that the NAS6604-15 bolts were installed and to determine if any of the nuts may have been the missing nut.

The received nuts were examined in the ATSB laboratories with the measurements and observations recorded (Table A4). Due to fire damage, some of the markings on a number of the nuts were unable to be determined.

Table A4: Evaluation of various nuts

SampleHeight (in)Width (flats) (in)Material/markings
MS21042L4/NAS12910.204-0.2190.304-0.316Alloy steel, grade 1035, 1042, 1050, 4027, 4037, 8630 or 8740. Cadmium plated
D210-4 nut Corrosion-resistant (CRES)0.205-0.2190.304-0.316Stainless steel alloy 660
VH-HGU remaining bellcrank nuts0.213 (5.4mm)0.309 (7.85mm)Alloy steel – 4037‘R’ on flats
A014-6 (2 of)0.215 (5.5mm)0.307 (7.8mm)‘R’ on flat
Nut found 16-5-20180.215 (5.45mm)0.311 (7.9mm)‘M’ on base
Nut and washer found 15-5-20180.213 (5.4mm)0.311 (7.9mm)‘M’ on base
Various fasteners, 2 of, small nuts0.258 – 0.275 (6.57 – 6.7mm)0.375 – 0.379 (9.52 – 9.62mm)No markings
Various fasteners, 2 of, large nuts0.280 (7.1mm)0.440 (11.17mm)No markings
Exemplar nut (from maintenance stock)0.2070.308‘c’ and ‘k’ on basevertical line on opposite flats

The forward support assembly (A014-6) was part of the landing gear, and the IPC showed that it should contain two NAS6604-15 bolts.[46] Due to fire damage, the markings on the heads of the two bolts from the forward support assembly were illegible. However, the bolts were measured and the results consistent with the requirements for a NAS6604-15 bolt Table A5.

Table A5: Results from bolt examinations

 Width
(flats) (in)
Shank diameter
(in)
Thread length
(in)
Grip length
(in)
Length
+/-0.015 (in)
Height
(head) (in)
NAS6604-15 bolt0.429-
0.439
0.2485-
0.2495
0.4250.9381.3630.125
A014-6 bolts11.16mm (0.439in)0.2490.4290.93534.74mm (1.368in)0.126

Jackshaft

Maintenance records showed that the jackshaft had undergone maintenance, including non‑destructive testing, on or around 25 May 2017 during the 2,200-hour overhaul. The testing involved the removal of the fasteners, and as per the R22 service letter SL-64, updated IPC and maintenance manual, the nuts on the jackshaft should have been changed to the new D210‑series nuts at this time.

Examination of the four nuts showed them to be similar to those remaining in the bellcrank. Specifically, they were of a similar size, and three of them exhibited the same markings ‘R’ on the flats (Figure A14). Due to heat damage, no markings were able to be resolved on the fourth self-locking nut. Analysis of the four nuts from the jackshaft assembly was performed using the EDS and showed that all four nuts were consistent with a carbon/alloy steel, not stainless steel. The geometry, markings and chemistry indicated they were MS21042-L4/NAS1291-series nuts.

Figure A14: Jackshaft assembly (left) and magnified view of one of the nuts (right)

Figure A14: Jackshaft assembly (left) and magnified view of one of the nuts (right).
Source: ATSB

Source: ATSB

Discussion

Separation of the fastener from the bellcrank

The investigation considered when separation of the fastener from its installed position within the bellcrank was likely to have occurred. A number of observations indicated that the fastener was not in position at the time of the impact with the ground:

  • There was an absence of significant physical damage to the bolt holes where the bolt was missing and surrounds. That is, no gross deformation or elongation of the holes to indicate that the fastener assembly had been forcibly removed during the accident sequence.
  • The bellcrank and torque tube fork assembly had been subject to significant mechanical damage such that the rod ends had fractured in overstress and the left side of the yoke assembly and bellcrank plate had significantly distorted. While the distortion of the plates was similar where the fasteners remained in position, the plates had been pushed together where the fastener was missing.
  • Rippling was observed on the internal surfaces of the bolt hole, considered to be evidence of heat damage, and the bellcrank was twisted/distorted such that a new bolt was unable to be inserted into the hole. The two remaining bolts could be easily reinserted into their respective holes following removal.
  • Yellow colouration was present on the inside of the bellcrank around the two fasteners that had remained in position. This was likely from the oxidised cadmium plating from the installed hardware including nuts, bolts and washers. No such colouration was observed around the internal surfaces of the bellcrank holes where the fastener was missing. This indicated that the bolt and associated hardware was not in position at the time of the post-impact fire. A minimal amount of residue was observed around the hole on the nut side of the bellcrank, likely from material transfer from the lock washer. This suggested the fastener had been previously installed.

Bellcrank – the missing fastener

A solitary bolt excavated from the accident site and submitted by the next-of-kin exhibited the markings of a NAS6604-15 bolt. It also exhibited the same manufacturing mark as that on the other bolts fitted to the bellcrank. As all the other NAS6604-15 bolts were accounted for—on the bellcrank, forward support assembly, main rotor head yoke assembly and inside main rotor blades —it was very likely that this was the missing bolt from the bellcrank. The bolt was in relatively good condition, and except for thermal effects from the post-accident fire, it showed no damage on the head, shank or threads. One small groove was observed on the second to third thread flank, which was potentially from engagement with a self-locking nut during assembly. There did not appear to have been any galling or thinning of the threads, which is damage that would be expected from multiple installations of a MS21042-L4 nut.

Jackshaft

Examination of the jackshaft assembly recovered from the wreckage of VH-HGU showed that three of the four nuts had the same manufacturer markings to the nuts in position on the bellcrank. There were no discernible markings on the fourth nut. The same manufacturer’s mark was also observed on the forward support assembly, and it was considered very likely that the nuts were original from manufacture.

The ATSB’s chemical analysis of the nuts confirmed that all four were consistent with a carbon/alloy steel. Though the analysis was semi-quantitative, the spectrographs of the four nuts were inconsistent with the CRES (corrosion resistant – stainless steel) D210-4 nuts specified in the Robinson R22 IPC. The nickel, chromium and molybdenum additions, where detected, were not of sufficient quantity to designate the nuts as stainless steel. The nuts fitted to the jackshaft were therefore likely MS21042-L4/NAS1291-series nuts.

Conclusion

The following is a summary of the main findings made during examination of the bellcrank and associated components, other recovered items and the jackshaft from VH-HGU:

  • Due to the observed damage on the bellcrank and torque tube fork assembly, the horizontal push-pull tube fastener assembly was not in position at the time of the impact with terrain.
  • The remaining bolts from the bellcrank were consistent with a NAS6604-15 bolt and the nuts were consistent with an MS21042L4/NAS1291-series nut.
  • The solitary bolt found on 16 May 2018 was consistent with an NAS6604-15 bolt, and had the same manufacturer mark as the bolts that had remained in position. As the other NAS6604-15 bolts were accounted for, it was very likely that this was the missing bolt from the bellcrank.
  • The self-locking nut from the missing bellcrank fastener assembly was not recovered in the wreckage, including in the pieces of metallic debris when dissolved.
  • The nuts on the jackshaft assembly were not changed to D210-4-series nuts as per the Robinson instructions for continued airworthiness when they were removed to perform non‑destructive testing on the jackshaft (part number A337-1) during the 2,200-hour overhaul.

Appendix B – Maintenance workload

Figure B1 and Figure B2 depict the progression of the 100-hour inspections (yellow) and 2,200‑hour overhauls (green) by Cloncurry Air Maintenance for the Cloncurry Mustering Company in the month prior to and following the accident (red).

Figure B1: CAM maintenance jobs for CMC in July 2017
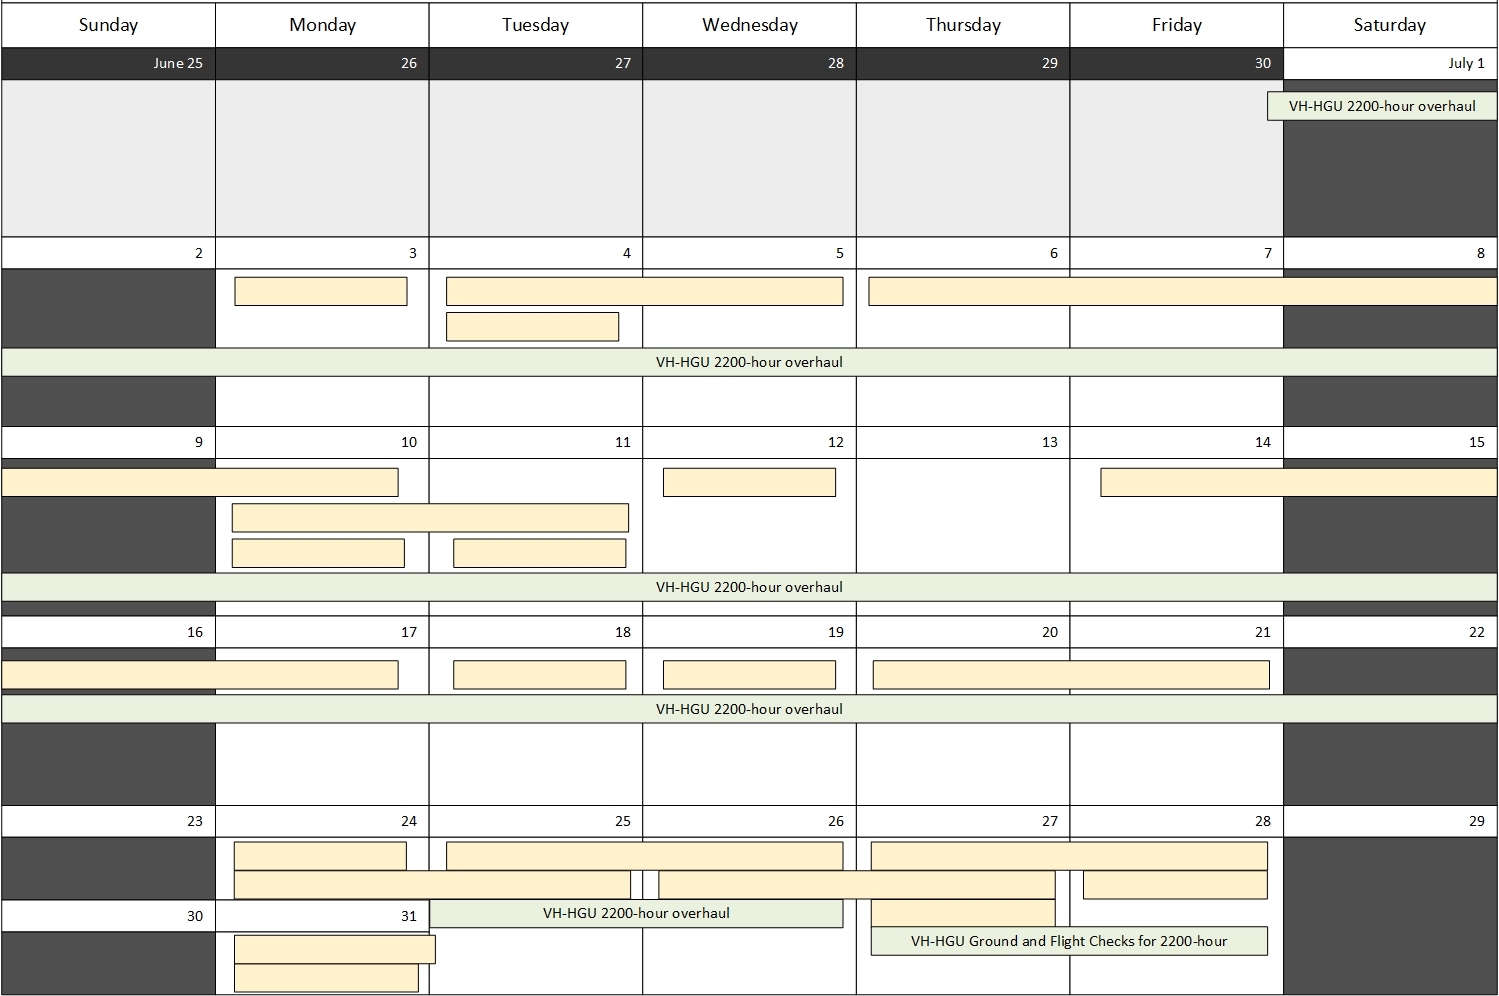
Figure B1: CAM maintenance jobs for CMC in July 2017.
Source: ATSB

Source: ATSB

Figure B2: CAM maintenance jobs for CMC in August 2017
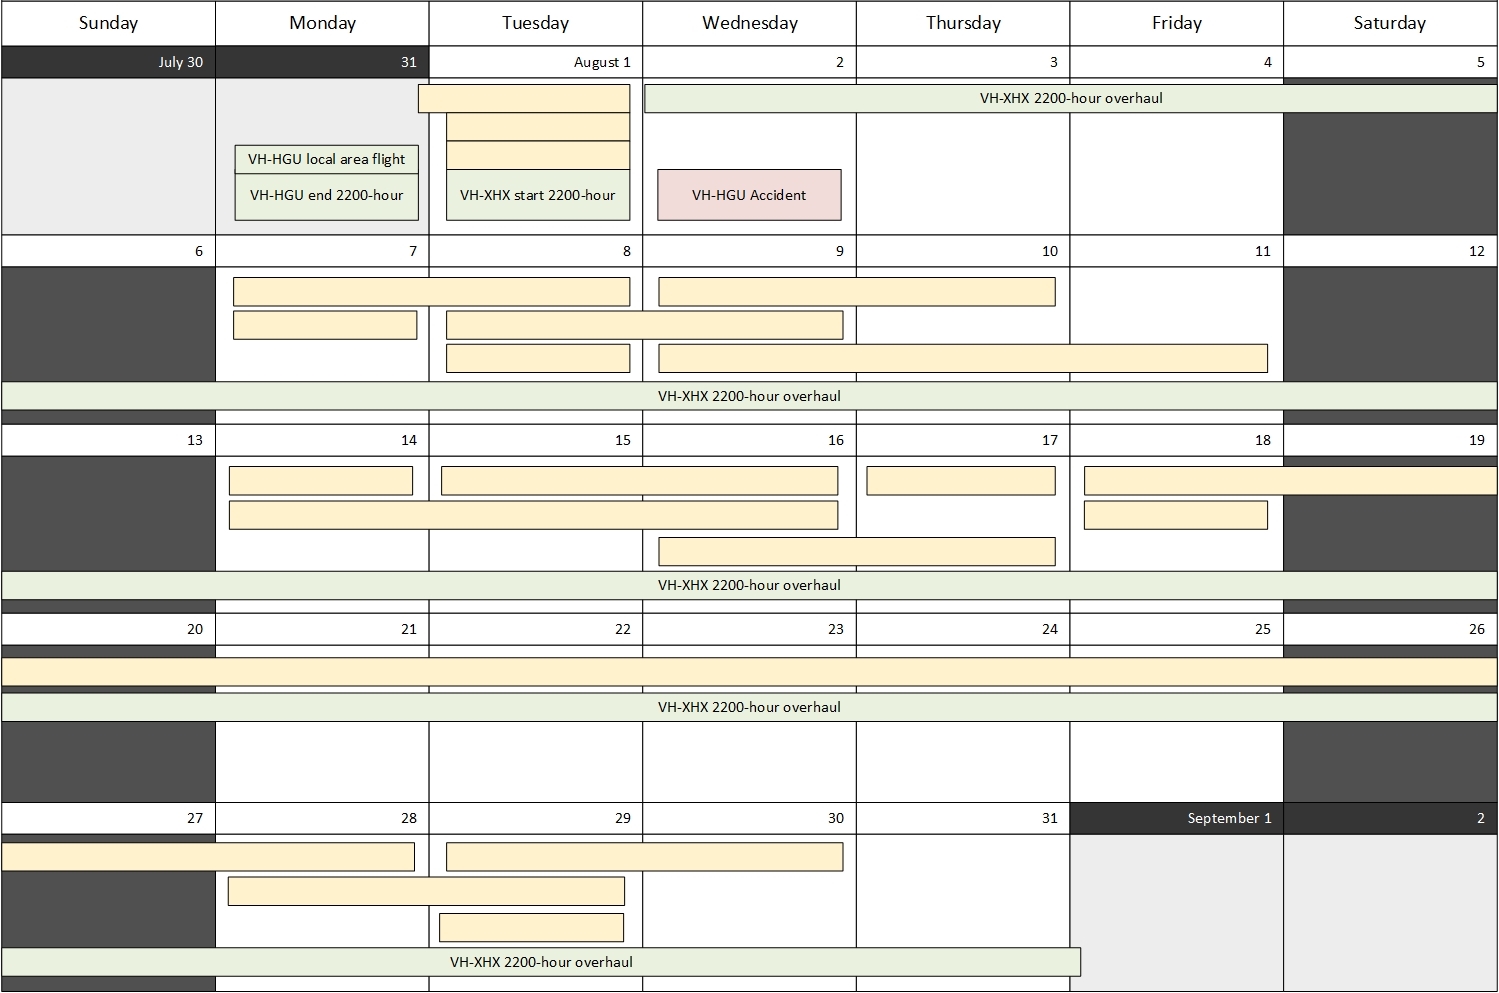
Figure B2: CAM maintenance jobs for CMC in August 2017.
Source: ATSB

Source: ATSB

__________

  1. National Aerospace Standard, NAS6603 thru 6620, Bolt, tension, hex head, close tolerance, alloy steel, long thread, reduced major dia.,self-locking and non-locking, 160 KSI Ftu , Revision 8, June 12, 2009.
  2. Galling: a form of wear caused by adhesion between sliding surfaces.
  3. Radiography was performed by the National Laboratory for X-ray Micro Computed Tomography (CTLab) at the Australian National University.
  4. RHC indicated there were six NAS6604-15 bolts on the R22; three in the cyclic control bellcrank, two in the forward support assembly, and one (of variable length, but possibly a -15 bolt) within the main rotor swashplate. The swashplate bolt was not normally accessible, but was observed in position by ATSB investigators.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2020

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2017-078
Occurrence date 02/08/2017
Location 7 km north-north-west of Cloncurry Airport
State Queensland
Report release date 21/07/2020
Report status Final
Investigation level Systemic
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight control systems
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22 Beta
Registration VH-HGU
Serial number 4335
Aircraft operator Cloncurry Mustering Company
Sector Helicopter
Operation type Aerial Work
Departure point Cloncurry Airport, Queensland
Destination Cloncurry Airport, Queensland
Damage Destroyed

Safeworking irregularity involving Lookout Working, near Tempe, New South Wales, on 31 July 2017

Final report

Report release date: 25/07/2019

Safety summary

What happened

On 31 July 2017, a team of Sydney Trains’[1] infrastructure maintainers were conducting a series of inspections and measurements along the Up and Down[2] Illawarra Main and Up and Down Illawarra Local lines, Tempe. The workgroup were located between 746 points and 748 points when a passenger service 59-J travelling on the Down Illawarra Local line towards Tempe Station narrowly missed the workgroup as it passed their worksite. There were no injuries or damage.

What the ATSB found

The workgroup had relied on lookout working (LOW) as the method of worksite protection. Two workers were positioned as lookouts for oncoming trains; one trackside watching for the approach of Down trains, using track warning lights[3] (Down lookout), the other positioned at Tempe[4] Station footbridge watching for the approach of Up trains (Up lookout). The Down lookout had diverted his attention away from the warning lights to acknowledge an Up train. When he re-focussed on the warning lights, he realised a warning light for approaching Down trains had extinguished. He was not able to sound a warning to the workgroup and give them sufficient time to clear the danger zone to a safe location, before 59-J approached their location.

Additionally, the ATSB found the location of the worksite was considered unsuitable for LOW according to Sydney Trains’ Worksite Protection and Hazardous Locations Register (WPHLR).

What's been done as a result

On 12 November 2017, Sydney Trains made changes to NPR 711 Using Lookouts[5]. Instructions mandated that warning lights must not be used to provide warning of approaching rail traffic when using lookouts. Further, this instruction applied to all tracks in the Sydney Trains Network unless specifically exempted in the Network Local Appendices.

Sydney Trains is also reviewing the WPHLR with a view to simplifying the document by only including locations where LOW is specifically prohibited.

Safety message

Compared to the other worksite protection methods, Lookout Working (LOW) does not warn, or restrict trains from approaching, or entering a work location. Where practicable, rail transport operators (RTOs) must require track workers to continually re-assess the site risks, add/combine safety measures (like Automatic Track Warning System, or audible warning devices), or implement a higher form of protection.

__________

  1. All trains, employees, roles, Network Rules, Network Procedures and maintenance responsibilities referred to in this report were under the control of Sydney Trains.
  2. Trains that travel away from Sydney are Down trains. The lines that carry them are Down lines. Trains that travel towards Sydney are Up trains. The lines that carry them are Up lines, e.g., ‘Up and Down Main’ Lines.
  3. A track warning light is defined as an illuminated white or orange warning light provided at locations where workers on track have a restricted view of approaching rail traffic. If rail traffic approaches, the light goes out, giving time for workers to move to, or remain in, a safe place (Network Rule NSG 604).
  4. The rail kilometrage for Tempe Station is 6.770 km by rail South of Central railway station. This was referenced from Network Local Appendices NLA 402.
  5. These changes were advertised on the RailSafe website and cited Safe Notice 1042-2017 (which outlined the specific change to NPR 711 Using Lookouts) and SafeTracks 3 November 2017 (which provided more information about the changes). Refer to www.railsafe.org.au/


The occurrence

What happened

On the morning of 31 July 2017, a team of four Sydney Trains infrastructure maintainers from their Sydenham Network Base gathered to conduct a series of regular inspections and measurements at several points along the Up and Down Illawarra Main and Up and Down Illawarra Local lines, Tempe. The work involved four sets of points, with the incident occurring between 746 points and 748 points (see Figure 1).

Figure 1: Incident location – Tempe, NSW

Figure 1: Incident location – Tempe, NSW. Source: ATSB

Source: ATSB

Two workers forming an inspection team, entered the danger zone and accessed the track in accordance with procedures for the protection of track workers using Network Rule NWT 310 Lookout Working. The rules stipulated that all workers and equipment were to be completely within a safe place a minimum of ten seconds before rail traffic entered a worksite (passed their location).

At approximately 1000, empty passenger service 59-J was travelling on the Down Illawarra Local line towards Tempe Station, when the driver observed the workgroup in the danger zone. The driver applied the train brakes, blew the horn and the workers began to move off the line towards a safe place, to the side of the track or ‘cess’ (see Figure 1). A review of CCTV footage from the train showed that the workers had nearly reached a safe place when the train passed the workers’ location (approximately seven seconds after the train first observed the work group). There were no injuries or damage.

The incident involving train 59-J occurred when the Down lookout responded to the horn from the approaching Up train. He turned away from the warning lights to provide an ‘all clear’[6] hand signal to the driver of the Up train. He then waited for an acknowledgement from the driver of the Up train, before turning back to re-focus on the warning lights. He realised a warning light for approaching down trains had already extinguished. He was not able to sound the warning to the work group and give them sufficient time to clear the danger zone to a safe location, before 59-J approached their location.

__________

  1. Drivers or Track Vehicle Operators must sound the whistle to acknowledge an ALL CLEAR handsignal given by a white light, or one hand held high (Network Rule NGE 202).

Context

Location

The incident location at Tempe is approximately 6.5 km from Sydney’s Central Station and is a multiple-track site consisting of the Up and Down Illawarra Main and Up and Down Illawarra Local lines.

Figure 2: Location of Tempe Station, NSW

Figure 2: Location of Tempe Station, NSW. Source: Google Maps

Source: Google Maps

Worksite protection

Network Rule NWT 300 Planning Work in the Rail Corridor requires work in the danger zone to be planned and carried out using one of five methods of worksite protection[7]. The different methods of worksite protection are implemented according to the risk involved with the work task.

LOW is relatively expedient to implement compared to other worksite protection methods. This is because LOW does not prevent trains from entering the worksite. Protection of workers under LOW is reliant on positive outcomes from human performance and compliance to procedures.

To minimise risk, the Network Rules encourage track workers to assess and reassess the risks at each location, apply additional safety measures, or implement a higher form of protection, where practicable. NWT 300 states that Local Possession Authorities (LPAs) and Track Occupancy Authorities (TOAs) are the preferred methods of working on track, mainly as they authorise closure, or exclusive occupation of the track. The LOW rule, NWT 310, reinforces this philosophy when it states:

‘If Absolute Signal Blocking (ASB) is available, it is preferred over Lookout Working’.

Some considerations in reducing risk when using LOW are to add, or combine, additional safety measures like Automatic Track Warning System (ATWS), or audible warning devices.

LOW network procedure

Lookouts are responsible for maintaining minimum allowable sighting distance, remaining vigilant for and detecting the approach of trains, and for warning workers in the danger zone of an approaching train.

The LOW Network Procedure NPR 711 states lookouts must:

  1. Agree with the Protection Officer on how workers will be warned about the approach of rail traffic.
  2. Stand in a safe place where you can see approaching rail traffic and be within sight and hearing of the workers. If you cannot do both of these safely, tell the Protection Officer.
  3. Keep a continuous lookout for the approach of rail traffic.
  4. When rail traffic approaches, warn the workers immediately.
  5. Only if workers and their equipment are in a safe place, face the approaching train or track vehicle and give the ALL CLEAR handsignal to the Driver or Track Vehicle Operator.
  6. Wait for the Driver or Track Vehicle Operator to acknowledge the ALL CLEAR handsignal.
  7. Make sure that the line is clear before telling the Protection Officer that it is safe for work to resume.
  8. Tell the Protection Officer if you need to move from your designated position. Do not move from your position until:
    - all workers and their equipment are in a safe place
    - a new Lookout is in position
  9. Tell the Protection Officer if conditions such as visibility change.

The Network Rules do not stipulate any separate criteria for trains approaching from one direction or another direction.

Location of the Lookouts

The distance of the work group at 746 points from the Up lookout was approximately 350 metres. The distance of the work group from the Down lookout from 746 points was approximately 170 metres. At these locations the Down lookout was within sighting distance of the work group, however, the sighting distance to the Up lookout was obstructed by the overhead bridge stanchions.

Figure 3: View from the position of the Down lookout

Figure 3: View from the position of the Down lookout. Source: ATSB

Source: ATSB

Figure 4: View from the position of the Up lookout, looking towards the work group

Figure 4: View from the position of the Up lookout, looking towards the work group. Source: ATSB

Source: ATSB

Worksite Protection Hazardous Locations Register (WPHLR)

The Worksite Protection Hazardous Locations Register (WPHLR) identifies hazardous locations across the Sydney Trains rail network. Its purpose is to help users understand the hazards relating to worksite protection in these hazardous locations and provide recommendations for implementing appropriate worksite protection.

This section of track was included on the WPHLR and was considered an area inappropriate for using LOW. The Up Main and Down Local Illawarra lines were the two inside rail lines of the four rail line corridor. These tracks were identified to have some areas with inadequate sighting distance or no safe place. The recommended precautions were:

‘Unless a safe place can be created by taking an ASB on the adjacent track to which the worksite is to be set up, LOW is not permitted’

This WPHLR was available and was consulted by the Protection Officer (PO), who considered the WPHLR as a guide only. The protection plan was put to the Network Controller and was accepted, confirming the PO’s thoughts on the WPHLR.

Warning lights

In the network rule NSG 604 Indicators and signs, warning lights are described as;

Illuminated white or orange warning lights are provided at locations where workers on track have a restricted view of approaching rail traffic. If rail traffic approaches, the lights go out.

These lights can provide a warning to workers of approaching rail traffic. On detection of approaching rail traffic, the warning lights extinguish. This is intended to provide a fail-safe operation such that, if the light fails, or is observed to be extinguished, it must be assumed that a train is approaching.

The warning lights used by the Down lookout were illuminated white with a configuration of the example warning light in Figure 5.

Figure 5: Example of Warning light

Figure 5: Example of Warning light. Source: Sydney Trains

Source: Sydney Trains
__________

  1. The five include Local Possession Authority (LPA), Track Occupancy Authority (TOA), Track Work Authority (TWA), Absolute Signal Blocking (ASB) and Lookout Working (LOW).

Safety analysis

Mobile worksite and re-assessment of risk

Although the work itself was considered routine, the worksite area was mobile; that is, it was progressing along the rail corridor/tracks in the danger zone. The constantly changing terrain required the workers to be on both Up and Down tracks simultaneously and on multiple occasions. Both Up and Down lookouts were equipped with the same audible devices (horn and whistle) to warn the work group. In some cases, as in this incident, the position of the work group changed, whilst the position of the lookouts remained static.

In this incident, there were occasions when the workers passed through locations where there was restricted sighting (due to structures) and/or an absence of a safe place. It was likely that the ability of the lookouts to maintain sighting distance and provide timely warnings over the entire worksite area was impacted by the mobility of the work group conducting their inspection tasks.

Network Rule NWT 310 requires POs to reassess safety measures if conditions such as visibility, or work locations change. Additionally, if worksites are established over a large area, minimum warning times (MWTs) must be continually reassessed.

While the nature of the task required the workgroup to move over a large area and potentially affect MWT for the workgroup, there was no evidence of the PO reassessing MWTs.

The PO and Down lookout took on their respective roles at short notice, as other staff to fulfil these roles were not available. The PO also acted as the worksite supervisor and accompanied the inspection worker in the danger zone. The PO was satisfied that these additional duties did not interfere with his primary duty as a PO.

When interviewed, the PO explained his understanding of LOW and safe places. He expressed that when LOW was implemented over multiple rail tracks, safe places were created on adjacent clear rail tracks when a train approached on the same rail track as the workers.

The PO’s understanding of a safe place is not consistent with the definition of a safe place as defined in the RailSafe Glossary which states a safe place to be;

‘A place where workers and equipment cannot be struck by rail traffic.’

When a worker is on a live rail track there is a possibility of the worker being struck by rail traffic. Although the PO had been in the rail industry for 24 years and had worked as a qualified PO for 16 years, his understanding of a safe place in the rail corridor was no longer consistent with the definition.

The two lookouts and the inspection worker all agreed to the worksite protection plan and agreed with the PO on what constituted a safe place. It is likely the understanding of what constituted a safe place amongst all these workers increased the risk to the workers in the danger zone of being struck by rail traffic.

Responsibilities of the lookout

At Tempe, the Down lookout focused on acknowledging, by giving an ‘all clear’ hand signal and waiting for acknowledgement from an Up train. The Up train did not pose an immediate risk to the work group. The Down lookout focusing on acknowledging an Up train increased the risk to the work group of being struck by the Down train.

Where a lookout is required to remain vigilant for trains coming from a specific direction and provide adequate warning to people to get off the track, any distraction from this task increases the risk to the workgroup. NPR 711 stipulates that the lookout can only do this when workers and equipment are in a safe place, the ability for any lookout to perform this task effectively is questionable as the lookout must be able to establish the workgroup is clear of the track and will remain clear of the track before acknowledging the oncoming rail traffic.

There is limited time for a lookout to be satisfied of this when communication between the lookout and the workgroup is limited to non-verbal and visual communications. The act of acknowledging the oncoming train requires the lookout to face away from the workgroup and focus their attention on the oncoming train. The lookout cannot be sure members of the workgroup are clear and will remain clear when they turn away to acknowledge an oncoming train.

The Down lookout had the necessary competencies and experience to fulfil the role of a lookout. When interviewed, the Down lookout readily recalled the key responsibilities of that role and how they applied to the Tempe location. Notably, he explained that his decision to react to a train horn and provide an ‘all clear’ towards an Up train, was based on his interpretation and understanding of Network Rule NPR711 and from his practical experience. He reiterated that he reacted the same way to any train driver that sounded their train horn. This had been reinforced during his many years of track work experience, where he had personally received adverse reactions from drivers when they were not in receipt of an appropriate ‘all clear’ hand signal from lookouts.

Location of the Lookouts

The distance of the work group at 746 points from the Up lookout was approximately 350 metres. The distance of the work group from the Down lookout from 746 points was approximately 170 metres. At these locations the Down lookout was within sighting distance of the work group, however, the sighting distance to the Up lookout was obstructed by the overhead bridge stanchions.

The location and distance of the Up lookout from the work group would have made it difficult for the work group to hear the audible warning devices during their first two point inspections of 746 points and 748 points (see Figure 4).

Other ambient noise in closer proximity to the work group may have masked the sound of the horn and/or whistle which were the agreed audible devices used by the lookouts. Additionally, the overhead bridge between the Up lookout and the workgroup may have buffered the sound of the horn and whistle, making it harder for the work group to hear the audible warning. It is likely the audible warning devices would have been heard from the Down lookout.

The Down lookout was on the Up side of the work group during the inspections of 746 and 748 points. It is possible the Down lookout’s audible alarm coming from the Up side of the work group could have confused workers and delayed their evacuation from the danger zone. In most cases, Lookouts are on the extremities of the workgroup, so audible warnings from a lookout generally come from the direction the train is coming from.

Worksite Protection Hazardous Locations Register (WPHLR)

Had the WPHLR been a document that required strict adherence, then the Network Controller should have informed the PO and an alternate protection method would have been sought.

Reference and adherence to the WPHLR is not apparent in the Network Rules and Procedures. Having a reference such as this is useful, but only if relevant people are aware of and are required to use it when planning work site protection.

Use of warning lights

From the approaches to the worksite at Tempe, there are a number of obstructions affecting visibility of the workers from an approaching train. From the down direction, these include an overbridge, stanchions and track curvature towards the Sydney end. Due to the restricted sighting on these track approaches, two illuminated white warning lights were provided for the Down Illawarra and Down Illawarra Local lines near Tempe to assist lookouts.

This warning light system, which relied on a lookout maintaining active observation, was utilised by the Down lookout as the Protection Officer considered the risk associated with using LOW had been successfully mitigated by using the warning lights. The warning lights are not designed with backup mechanisms (such as audible alarms, additional lights) to alert persons in the vicinity that the light/s in fact had extinguished and warned of an approaching train. However, while the purpose of warning lights is included in the Network Rules (NSG 604), they do not stipulate their application to specific worksite protection methods, like LOW. The warning lights at this location were not shown on older diagrams/network maps, worksite protection planning diagrams (WPPDs)[8], or Drivers Route Knowledge Diagrams (DRKDs).[9] The PO used DRKDs when implementing LOW.

__________

  1. The RailSafe website stated that Worksite Protection Planning Diagrams (WPPD) were established to support the Rail Corridor Safety Program and were generated from the Sydney Trains Infrastructure GIS (Geospatial Information System). These were organised into books with each book covering a part of the Sydney Trains Infrastructure Network. These were uncontrolled documents and all information should be verified in the field. Refer to www.railsafe.org.au/diagrams
  2. The RailSafe website stated that Drivers Route Knowledge Diagrams (DRKD) were a stylised diagram showing the layout of major infrastructure in the Sydney Trains Network approved for train crew knowledge only. These were uncontrolled documents and all information should be verified in the field. Refer to www.railsafe.org.au/diagrams

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.

  • The incident involving train 59-J occurred during lookout working, when the Down lookout faced an approaching Up train to provide an ‘all clear’ hand signal to the train driver. At this time the Down lookout missed the change in aspect of the warning light indicating the approach of train service 59-J and could not provide adequate warning to the work group.
  • The Workgroup’s understanding and establishment of a safe place increased their risk of being struck by rail traffic.
  • The Down lookout’s interpretation and understanding of NPR711 contributed to his acknowledgment of the Up train.
  • The location and distance of the Up lookout from the work group may have made it difficult for the work group to hear the audible warning devices during their first two point inspections of 746 points and 748 points.
  • The location of the Down lookout presented a possibility of work group members being confused and delayed in responding to an audible warning.
  • Lookout Working (LOW) was implemented in an area deemed unsuitable for LOW on the Sydney Trains Worksite Protection Hazardous Locations Register (WPHLR). This is likely due to the WPHLR not being clearly stated as a reference with specific requirements that must be adhered to. [Safety issue]
  • Warning lights were utilised at Tempe to overcome sighting hazards and justify the use of LOW. Warning lights rely on lookouts maintaining continuous observation and their use were not specifically referenced in the LOW Network Rules. [Safety issue].

Safety issues and actions

The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.

Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the rail industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.

All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.

Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.

Use of warning lights

Safety issue number: RO-2017-009-SI-01

Safety issue description: Warning lights were utilised at Tempe to overcome sighting hazards and justify the use of Lookout Working (LOW). Warning lights rely on lookouts maintaining continuous observation and their use were not specifically referenced in the LOW Network Rules.

Single source of information for Lookout Working prohibition

Safety issue number: RO-2017-009-SI-02

Safety issue description: Lookout Working (LOW) was implemented in an area deemed unsuitable for LOW on the Sydney Trains Worksite Protection Hazardous Locations Register (WPHLR). This is likely due to the WPHLR not being clearly stated as a reference with specific requirements that must be adhered to.

__________

  1. These changes were advertised on the RailSafe website and cited Safe Notice 1042-2017 (which outlined the specific change to NPR 711 Using Lookouts) and SafeTracks 03 November 2017 (which provided more information about the changes). Refer to www.railsafe.org.au/

ATSB SafetyWatch

Safe work on track

The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. SafetyWatch provides information about each safety concern, and strategies to help manage risk areas, along with links to safety resources. One priority is ‘safe work on track’.

The ATSB has investigated several accidents that have occurred when maintenance work was being carried out on or near railway tracks. Conducting work on or near a railway track can be dangerous if safeworking rules and procedures have not been correctly implemented to protect the worksite. Trains cannot stop quickly and any breakdown in the communication or management of a worksite can leave workers extremely vulnerable to dangerous situations.

What can you do

Operational safe working on track requires a high level of preparation and organisation. Whenever there is work taking place on or near a track, coordination and communication are essential to ensure adequate worksite protection is implemented. Before authority is granted to occupy or work near a track, it is essential that all information is clearly communicated and verified between the Protection Officer and the Network Control Officer.

An adequate briefing about the work site and effective communications equipment must be made available to the track workers. For track workers, it is vital to ensure that all levels of worksite protection have been fully implemented before commencing work on or near the track.

Similarly, before worksite protection is removed, it is essential that the Protection Officer and the Network Control Officer ensure all plant and workers have ceased operating and are positioned clear of the track.

ATSB comment

Safe work on track across Australia

The ATSB has also produced a safety issue investigation report, Safe work on track across Australia: Analysis of incident data, 2009 – 2014 (RI-2014-011), that is available from the ATSB website. This safety issue investigation reviews available data from across Australia of incidents and accidents relating to work on track. It is designed to provide industry with insights into the protection arrangements that are failing, and the reasons why, across many occurrences so that safety action can be designed to reduce future safe work on track occurrences.

To minimise risk, rail transport operators must ensure systems for safe work on track encourage workers accessing the rail corridor to communicate sufficient information to validate their worksite location, the adequacy of the protections in place, and their positioning in relation to any approaching train movements.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2019

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number RO-2017-009
Occurrence date 31/07/2017
Location Near Tempe
State New South Wales
Report release date 25/07/2019
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Rail
Rail occurrence category Safe Working Irregularity/Breach
Occurrence class Incident
Highest injury level None

Train details

Train operator Sydney Trains
Train number 59-J
Type of operation Empty passenger service
Departure point Circular Quay, New South Wales
Destination Kingsgrove, New South Wales
Train damage Nil

Hard landing involving Gippsland Aeronautics GA-8, VH-MQI, Djamardi (Jimarda) ALA, Northern Territory, on 2 August 2017

Final report

Report release date: 17/11/2017

What happened

On 2 August 2017, a Gippsland Aeronautics GA-8 aircraft registered VH-MQI, was operated by Arnhem Land Community Airlines, as a charter passenger flight from Milingimbi, Northern Territory (NT) to Djamardi aeroplane landing area (ALA),[1] NT. There was a pilot and five passengers on board.

At about 1225 Central Standard Time (CST), the aircraft joined the downwind leg of the circuit for runway 10 at Djamardi. The pilot observed the windsock indicating a light north-easterly wind.

Recorded data captured the incident approach, along with three previous approaches, conducted by VH-MQI to runway 10 during earlier flights to Djamardi. The data shows that on the incident approach, the aircraft turned onto the base leg of the circuit earlier than these three previous approaches (Figure 1).

After turning onto the base leg, the pilot believed the aircraft was becoming high on the desired approach path and reduced power to return to the desired path. After turning onto the final leg of the circuit, the pilot stabilised the aircraft at the selected approach speed of 65 kt with a rate of descent of about 500 feet per minute.

Figure 1: Representation of recorded data showing the tracks of four approaches, including the incident approach, made by VH-MQI to runway 10 at Djamardi ALA. The downwind, base and final legs of the circuit for runway 10 are also shown.

Figure 1: Representation of recorded data showing the tracks of four approaches, including the incident approach, made by VH-MQI to runway 10 at Djamardi ALA. The downwind, base and final legs of the circuit for runway 10 are also shown.

Source: Operator, annotated by ATSB

At about 1227 as the aircraft approached the runway at a height of about 50 ft, the pilot observed the airspeed reduce to 62 kt and lowered the nose to accelerate the aircraft. The pilot did not recall increasing power. Recorded data shows that at this time, the descent rate increased to 846 feet per minute. The pilot detected the increasing descent rate and flared the aircraft more positively than normal, however he was unable to arrest the rate of descent. The aircraft touched down hard on the main landing gear. The cargo pod (Figure 2) struck the runway.

After the aircraft touched down hard, the aircraft bounced and became airborne. The pilot then increased power to attempt to stabilise the aircraft and continue the landing. The aircraft then touched down a second time, on the nose landing gear first, and again bounced. The pilot further increased power, stabilised the aircraft, and landed.

The pilot and passengers were not injured in the incident, the aircraft sustained minor damage.

Figure 2: VH-MQI showing the cargo pod fitted to the aircraft (left) and damage sustained during the incident (right).

Figure 2: VH-MQI showing the cargo pod fitted to the aircraft (left) and damage sustained during the incident (right).

Source: Operator, annotated by ATSB

Pilot comments

The pilot of the aircraft made the following comments:

  • In response to the reducing airspeed, instead of lowering the nose, power should have been increased.
  • Prior to landing, the approach did not feel out of control, or overly unusual. Only when the aircraft landed hard did he realise that it was an abnormal situation.

Operator report

The operator of the aircraft conducted an investigation in to the incident and provided the following observations:

  • The early base turn led to a steeper approach descent profile.
  • A change in wind direction from a north-easterly, to a northerly as the aircraft approached the runway, combined with mechanical turbulence caused by trees, increased the aircraft descent rate.
  • After the pilot detected the reducing approach speed, the technique used to accelerate the aircraft was incorrect. Engine power should have been immediately increased.
  • The cargo pod, both main landing gear legs and the fairings where the landing gear legs enter the fuselage were damaged (Figure 3). The right main landing gear leg was also cracked.

Figure 3: Damage to left main landing gear leg (left), and damage to the right main landing gear leg and fairing (right).

Figure 3: Damage to left main landing gear leg (left), and damage to the right main landing gear leg and fairing (right).

Source: Operator, annotated by ATSB

Safety analysis

Late in the final approach, the pilot detected the airspeed reduce below the desired speed. In response, the pilot lowered the nose of the aircraft. This led to a high descent rate which could not be arrested prior to the hard landing.

The hard landing damaged the cargo pod, the main undercarriage legs and fairings.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The incorrect response to the reducing airspeed led to a high descent rate with insufficient height to recover. This resulted in the hard landing and aircraft damage.

Safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Aircraft operator

As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:

Flight crew training
  • The pilot has received training in the correct technique to arrest a high rate of descent during approach and landing.
Guidance material
  • The operator’s guidance material for Djamardi ALA has been updated to include a note advising of possible turbulence due to the surrounding trees.

Safety message

This incident highlights the importance of maintaining the correct approach descent profile and speed, and ensuring that pilots respond correctly to any deviations from the desired profile.

The United States Federal Aviation Administration (FAA) Airplane Flying Handbook, chapter eight, Approaches and Landings contains the following guidance for pilots when approach speed reduces below the desired speed:

On the final approach, when the airplane is flown at a slower than normal airspeed, the pilot’s judgment of the rate of sink (descent) and the height of round out is difficult.

Whenever a slow speed approach is noted, apply power to accelerate the airplane and increase the lift to reduce the sink rate and to prevent a stall. This is done while still at a high enough altitude to re-establish the correct approach airspeed and attitude. If too slow and too low, it is best to execute a go-around.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

__________

  1. Djamardi ALA can also be known as Jimarda ALA.

Occurrence summary

Investigation number AO-2017-079
Occurrence date 02/08/2017
Location Djamardi ALA, (Jimarda ALA)
State Northern Territory
Report release date 17/11/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Hard landing
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Gippsland Aeronautics Pty Ltd
Model GA-8
Registration VH-MQI
Serial number GA8-TC 320-10-154
Aircraft operator Arnhem Land Community Airlines
Sector Piston
Operation type Charter
Departure point Milingimbi, Northern Territory
Destination Djamardi ALA, (Jimarda ALA), Northern Territory
Damage Minor

Flight below the minimum permitted altitude involving Pilatus PC-12, VH-FDJ, 19 km north-east of Adelaide Airport, South Australia, on 18 July 2017

Final report

Report release date: 18/12/2018

Safety summary

What happened

On the 18 July 2017, Pilatus PC‑12, registered VH-FDJ departed Alice Springs, Northern Territory for Adelaide, South Australia, on a routine single-pilot aeromedical patient transfer flight. During the approach into Adelaide, the pilot noted that the aircraft’s autopilot system failed to intercept the localiser for the Adelaide runway 23 instrument landing system (ILS) approach.

Unaware of why the autopilot did not intercept the localiser, the pilot then became focussed on determining the cause of the autopilot tracking issue while attempting to re-establish the aircraft back on the ILS to continue the approach. The pilot reported this resulted in high workload that was further increased by the tracking information displayed on the aircraft’s course deviation indicator not reflecting the position information being communicated by ATC.

The pilot continued the approach and commenced further descent after observing that the aircraft was close to becoming established on the localiser and that the glideslope was becoming active. Soon after, ATC notified the pilot that the aircraft was below the minimum permitted altitude for the aircraft’s position and instructed the pilot to climb the aircraft to a safe altitude. The pilot then conducted another ILS approach and landed.

What the ATSB found

The unexpected failure of the autoflight system to intercept and track the localiser resulted in the aircraft deviating from the surveyed instrument approach path and significantly increased the pilot’s workload.

The pilot’s focus on resolving the aircraft's lateral tracking and perceived autoflight issues during the localiser intercept decreased his attention on managing the aircraft’s approach profile. That led to the aircraft descending off-track below the minimum safe altitude.

Detection of the off‑track descent and subsequent intervention by the air traffic controller restored safe operation.

What's been done as a result

Following this incident, the operator amended their descent, arrival, and approach procedures, and training and checking procedures to be more prescriptive. In addition, the operator introduced dual global positioning systems, with moving map and chart overlay displays into their legacy aircraft, to improve pilot situation awareness.

Safety message

Adequate approach preparation, and management of aircraft flight profile and automation is vital to ensure pilots maintain manageable workloads and positional awareness during an approach. Additionally, pilots should not hesitate to conduct a go-around or a missed approach should the functionality of the aircraft’s automation, or the validity of positional information, be in doubt.


The occurrence

On the 18 July 2017 a Pilatus PC12, registered VH-FDJ, departed Alice Springs, Northern Territory, for a routine single-pilot aeromedical patient transfer flight to Adelaide, South Australia. The departure from Alice Springs and subsequent en-route phase of the flight was reported by the pilot to have proceeded normally.

Recorded data indicated that the aircraft reached the pilot’s calculated descent point from a cruise altitude of FL 250,[1] at about 42 NM (78 km) to the north-west of Adelaide Airport.

Before descending, the pilot reported that he obtained the available weather for Adelaide Airport and prepared the aircraft’s autoflight system for the arrival. This included programming the standard arrival route (STAR)[2] and instrument landing system (ILS)[3] approach frequency. The pilot also reported reviewing the respective arrival and approach charts displayed on the electronic flight bag screen.

At about 1240 Central Standard Time,[4] the aircraft left FL 250 to commence the Salty 1 STAR (Figure 1) and subsequently the runway 23[5] ILS. The pilot reported that as he was unfamiliar with the Salty 1 STAR, he elected to utilise the aircraft’s autoflight system and the Garmin 430 avionics system for navigation and descent.

Figure 1: Extract from the Adelaide Standard Instrument Arrival

Figure 1: Extract from the Adelaide Standard Instrument Arrival. Source:  Airservices Australia modified by the ATSB

Source: Airservices Australia modified by the Australian Transport Safety Bureau

The pilot reported that, during the descent, he noted a higher-than-normal groundspeed due to the strong westerly tailwind, however this decreased as the approach progressed to lower altitudes. As the aircraft approached the GLOBE waypoint, the pilot crosschecked the aircraft’s profile using the global positioning system (GPS) unit’s calculated profile. Noting that the aircraft was slightly high at that position, the pilot increased the selected descent rate on the autoflight system.

Just after passing the ELIZA waypoint and prior to turning inbound to intercept the localiser at GULLY, the pilot changed the primary navigation source from GPS navigation mode to a heading mode. This autoflight mode change was required to enable the pilot to set the inbound course for the ILS, to facilitate an intercept of the localiser for the runway 23 ILS approach. The pilot then recalled changing the autoflight system back to navigation mode to continue navigation to the waypoint GULLY and armed the approach mode for the ILS intercept. The estimated time available to complete these tasks was less than two minutes.

The pilot reported that the aircraft overshot the required intercept at GULLY. In response, he manipulated the autoflight system by turning the aircraft in the control wheel steering mode in an attempt to re-capture the localiser. At about that time, air traffic control (ATC) advised the pilot that the aircraft had flown through the localiser, ATC issued altitude and heading instructions to assist with a re-intercept. The pilot reported that this required him to cancel the current autoflight selections, including approach mode, to enable a heading to be selected and flown. The workload at this time was reported by the pilot to have been high as he attempted to determine the functionality of the aircraft’s autoflight and navigation systems.

Soon after, ATC gave the pilot radar information that positioned the aircraft left of the localiser. A clearance to conduct the ILS approach was then communicated, with a further request for the pilot to confirm when he was established on the approach. The pilot recalled that at that time he was still trying to determine the issues with the autoflight system and why the course deviation indicator (CDI) was giving conflicting information, indicating the aircraft was slightly right of the localiser. There was no recorded communication from the pilot reporting that the aircraft was established on the approach.

While trying to re-establish the aircraft on the localiser, the pilot observed the glideslope becoming active. As he believed that the aircraft was close to intercepting the inbound track, the descent was continued.

Recorded information confirmed that a short time later, ATC issued an altitude alert to the pilot to check his altitude. This was followed with instructions to climb to a new cleared altitude, to maintain the required terrain clearance, and to fly a different heading in anticipation of conducting another ILS approach.

The pilot reported that he followed the ATC issued radar vectors back to the commencement of the runway 23 ILS approach, where an intercept of the localiser using the autoflight system was made. The second approach was flown without issue.

Pilot information

The pilot was appropriately qualified for the flight, holding a Commercial Pilot Licence (Aeroplane). He also held an instrument rating for both multi-engine and single-engine aeroplanes. The pilot’s logbook recorded a total aeronautical experience of about 6,250 hours.

The logbook indicated that the pilot had about 5,800 hours in command of single-engine aircraft, which included about 640 hours flying Pilatus PC12 (PC12) aircraft.

The pilot had reportedly used the Garmin 430 avionics system before and had previous experience flying the PC12 legacy aircraft (see the section titled Operations). The pilots training file noted the pilot appeared to have no difficulty using the Garmin 430.

The appropriate flight reviews and proficiency checks had been conducted and the pilot was deemed competent to conduct line flying operations by the operator on the 5 July 2017.

The pilot held a valid class 1 aviation medical certificate and reported that he was well-rested prior to the flight and was in good health.

Weather

The pilot reported experiencing a strong westerly tailwind of about 57 kt during the descent and that the approach was conducted in instrument meteorological conditions. However, he noted that as the aircraft descended, the wind decreased and cloud layers were observed.

During the time of the aircraft’s arrival, the trend forecast for Adelaide Airport indicated a cloud base of 1,800 ft with broken cloud at 6,200 ft and wind from 280° M at 19 kt. There were also expected periods of up to 30 minutes duration where the weather would deteriorate, with the wind at 270° M at 22 kt gusting to 38 kt and the visibility reducing to 3,000 m in showers of rain.

Operations

The operator conducted aeromedical services throughout most regions of South Australia and the Northern Territory. The Pilatus PC12 aircraft was the only aircraft type used by the operator. The operator had three variants of the PC12, namely the PC12/45, PC12/47 and PC12/47E. The older PC12/45 and PC12/47 (sometimes referred to as the ‘legacy’) had different avionics and operating characteristics to the newer PC12/47E (referred to as the ‘NG’).

The operator had a valid Air Operator’s Certificate that enabled the use of PC12 aircraft in the charter and aerial work categories, which included the conduct of ambulance functions. The operator also had approval to conduct training and proficiency checks in accordance with the Civil Aviation Safety Regulations 1998.

The operator’s PC12 flight training manual provided basic reference material that related to initial pilot training. The flight training manual included an outline of the training syllabus, checklists and some lesson plans to assist the instructor with training preparation. The flight training manual did not provide any guidance to pilots as to the procedures and operational considerations while flying the PC12.

The flying operations manual outlined the standard operating procedures (SOPs) for a descent and approach. It included that:

At an appropriate time, the pilot is to review the intended approach procedure, including where applicable:

a. instrument or visual approach,

b. airfield information from ERSA, Jeppesen or OPS28 Airfield Register,

c. If an instrument approach procedure is required:

- correct chart, aids and frequencies,
- airfield elevation and MSA [minimum sector altitude],
- initial approach altitude and entry procedure,
- approach procedure,
- visual procedure - restrictions, runway, aircraft configuration, and
- missed approach procedure.

Checklists used by pilots during flight listed that an ‘approach review’ was to be completed before transition. It was reported by the operator that in the case of longer flights, such as Alice Springs to Adelaide, an approach review and flight instrument setup actions should be completed before commencing the descent.

There was no guidance for pilots as to the operator’s expected flight instrument settings for the arrival. However, the operations manual highlighted the importance of pre-arrival planning and flight instrument set-up during the approach/landing phase. It included procedures for the conduct of a non-precision approach (other than area navigation[6]), area navigation approach and precision approach. There was no guidance to pilots as to when an approach review/brief and flight instrument setup should occur.

The operators expected instrument setup for VH-FDJ (FDJ) differed from other PC12 aircraft in the operator’s fleet due to variation in FDJ’s avionics. The operations manual required that specific familiarisation training was required for pilots flying VH-FDJ due to the differences with all other aircraft in the fleet. The pilot had conducted in-flight training in FDJ prior to the incident.

It was reported by the operator that a pilot flying FDJ should ensure that the inbound course was set on the CDI prior to commencing the STAR. This would alleviate the requirement to change between navigation modes once the STAR had commenced. It would also reduce pilot workload during the descent and arrival.

Training

The operator conducted ground theory training, endorsements, and line training for pilots flying the PC12 variants. The PC12 fleet comprised nine of the newer (NG) type aircraft fitted with ‘glass cockpit’ avionics, and eight older (legacy) type aircraft, with different avionics and operating characteristics. Training provided pilots with familiarity of both types. The occurrence pilot had significant previous experience on the legacy PC12 so the major component of his in command under supervision (ICUS) training concentrated on the NG variant.

The operator’s flight training records identified that the pilot had successfully completed all components of the operators training syllabus. However, notes made during the training identified that the pilot had difficulty at times with profile management, and approach preparation. These issues were not apparent during the pilot’s final flight check for commencement of line operations.

The pilot completed about 96 hours of in-flight training before being approved to conduct line flying operations on the 5 July 2017. The training consisted of 28 training flights, which included 24 flights with the newer PC12 NG variant and four flights with the PC12 legacy aircraft.

Following this occurrence, the pilot completed six remedial flights, two of which were in legacy aircraft. Those flights identified that the pilot required additional training with approach preparation. This included conducting more thorough approach briefings and ensuring that the approach checks and setup were not left too late in order to avoid high workload situations. The pilot’s training notes also emphasised the importance of conducting a go-around if the approach became unstable. At the end of this training the pilot was re‑checked and resumed line flying operations.

Related occurrences

A database search identified a number of occurrences with aircraft descending below the minimum safe altitude. The occurrences have primarily involved aircraft on approach to land. They include situations where pilot(s) attention has been on other tasks during higher workload phases of flight, such as during the later stages of an instrument approach. The ATSB has published the following related safety investigation reports.

AO-2015-018: Flight path management and descent toward the lower limit of controlled airspace involving Airbus A320, VH-VND, on approach to Melbourne Airport, Victoria, on 11 February 2015

On 11 February 2015, an Airbus A320 aircraft, registered VH‑VND and operated by Tiger Airways, was conducting a scheduled passenger service from Hobart Airport, Tasmania to Melbourne Airport, Victoria.

At about 1750 Eastern Daylight-saving Time, about 9 NM (17 km) north of Melbourne Airport, and after the flight crew had been cleared by air traffic control to conduct a visual approach, the aircraft descended below the minimum safe altitude, though the aircraft remained in controlled airspace.

During the descent, both flight crew became preoccupied with other tasks inside the flight deck, which had the effect of increasing their workload and distracting them from monitoring the aircraft’s flight path and altitude. About two minutes after commencing descent on the visual approach, the flight crew levelled the aircraft after realising that it appeared to be low on profile. A safety alert issued by air traffic control soon followed and in response, the aircraft was climbed to intercept the recommended visual approach descent profile. The remainder of the flight was uneventful and the aircraft landed on runway 16 at Melbourne Airport.

AO-2016-012: Descent below segment minimum safe altitude during a non-precision instrument approach involving Airbus A320, PK-AXY, 17 km WSW Perth Airport, Western Australia on 19 February 2016

On the evening of 19 February 2016, an Airbus A320 aircraft, registered PK-AXY and operated by PT Indonesia AirAsia was on a scheduled passenger service from Denpasar, Indonesia to Perth, Australia. During cruise, the captain’s flight management and guidance computer (FMGC1) failed. Due to the failure, the flight crew elected to use the first officer’s duplicate systems. For the aircraft’s arrival in Perth there was moderate to severe turbulence forecast below 3,000 ft with reports of windshear. The crew commenced an ILS approach to runway 21.

During the approach, the flight crew made a number of flight mode changes and autopilot selections, normal for an ILS approach with all aircraft operating systems available. However, some of those flight modes and autopilot selections relied on data from the failed FMGC1 and the auto-thrust system commanded increased engine thrust. The crew did not expect this engine response and elected to conduct a go-around. With an increasing crosswind on runway 21, the crew accepted a change of runway, to conduct a non-precision instrument approach to runway 06.

With the time available, the first officer programmed the new approach into his FMGC and conducted the approach briefing. During this period, the captain hand flew the aircraft and manually controlled the thrust. During the approach to runway 06, the crew descended the aircraft earlier than normal, but believed that they were on the correct flight path profile.

While descending, both flight crew became concerned that they could not visually identify the runway, and focused their attention outside the aircraft. At about that time, the approach controller received a ‘below minimum safe altitude’ warning for the aircraft. The controller alerted the crew of their low altitude and instructed them to conduct a go-around. The crew then conducted another approach to runway 06 and landed.

__________

  1. Flight level: at altitudes above 10,000 ft in Australia, an aircraft’s height above mean sea level is referred to as a flight level (FL). FL 370 equates to 37,000 ft.
  2. Standard Instrument Arrival (STAR): A designated IFR arrival route linking a significant point, normally on an air traffic services route, with a point from which a published instrument approach procedure can be commenced.
  3. Instrument Landing System (ILS): A precision instrument approach system which normally consists of the following electronic components: VHF Localiser, UHF Glideslope and VHF Marker Beacons.
  4. Central Standard Time (CST): Coordinated Universal Time (UTC) + 9.5 hours.
  5. Runway number: the number represents the magnetic heading of the runway.
  6. Area navigation (RNAV): A method of navigation which permits aircraft operation on any desired flight path within the coverage of ground or spacebased navigation aids, or within the limits of the capability of selfcontained aids, or a combination of these.

Safety analysis

Approach preparation and management

A number of factors lead to the pilot not being fully prepared for the arrival and subsequent instrument landing system (ILS) approach to Adelaide Airport. Although the importance of early preparation and maintenance of an appropriate flight path profile was reinforced during the pilot’s line training, the impact of not fully configuring the aircraft’s instrumentation earlier in the approach was likely not recognised by the pilot. This, combined with the effect of a tailwind during the approach, reduced the available time for the pilot prepare for the localiser intercept.

While it could not be determined why the aircraft’s autoflight system did not capture and track the localiser, it was possible that a late setup of the inbound course and arming of the approach provided insufficient time for the autopilot to turn the aircraft. From the available evidence it was likely that the pilot had less than two minutes to setup the instrumentation, arm the approach and prepare for the intercept.

It is possible that during preparation for the approach, the pilot incorrectly set the reciprocal of the inbound course on the aircraft’s course deviation indicator (CDI), resulting in displayed tracking indications that were not in the command sense. That would account for the difference between the aircraft’s position, relative to the localiser, displayed to the pilot compared to that advised by air traffic control. That discrepancy created confusion over the aircraft’s actual position and, in combination with the unexpected overshoot of the localiser, significantly increased the pilot’s workload in managing the ILS approach.

The pilot became focussed on resolving the aircraft's lateral tracking and perceived autoflight issues during the localiser intercept. His recollection of being aware that the aircraft was descending but unaware of its specific altitude was consistent with decreased attention on managing the aircraft’s approach profile. That led to the aircraft descending off-track below the minimum safe altitude until identified and remedied by the positive actions of the controller.

Pilot workload

When the aircraft did not automatically intercept the localiser as expected the pilot’s workload started to increase.

Workload has been defined by Orlady & Orlady (1999) as ’reflecting the interaction between a specific individual and the demands imposed by a particular task. Workload represents the cost incurred by the human operator in achieving a particular level of performance’.

Each individual has a finite set of mental resources which allow them to process information and identify appropriate tasks. The set is a variable trait, and will vary with many factors including the experience, training, recency and familiarity with a situation, stress and fatigue. Harris (2011) stated ’High workload is associated with increased error rates (and hence an associated decrease in safety margins) as well as having the effect of reducing overall productivity and increasing occupational stress’.

When the workload gets too high for the available set of resources, an individual will start to task shed, initially systematically and eventually indiscriminately as the workload continues to increase. Green et al. (1996) identified, ‘as the demands of the task, or the workload, are increased, the standard of our performance is achieved. Any increase in workload after this point leads to an overall degradation in performance. At extremely high levels of workload (overload), important information may be missed due to the narrowing or focussing of attention onto only one aspect of the task.’

The United Kingdom Civil Aviation Authority publication CAP 737 (2016) states workload ‘is linked to almost all other areas within cognition and performance, particularly attention, vigilance, fatigue, skills, and multi-tasking.’

Approach and landing is a well-known period of high workload for pilots. In this occurrence, the following factors had the potential to increase the pilot’s workload:

  • an increased ground speed
  • limited recent experience with the autoflight system fitted to this aircraft type
  • the high intrinsic workload of single-pilot IFR flight
  • restrictions of the single-channel autoflight system in setting up the ILS instrumentation.

While the pilot had the correct intentions for the approach, once the error arose with the aircraft tracking, the pilot became unable to effectively monitor the approach while troubleshooting the situation. Following the intervention of air traffic control, the situation was resolved and the second approach was flown without issue.

Training

The pilot’s initial training with the operator appeared to address identified approach management issues by the time he was cleared to conduct line flying operations. Recognising that subsequent remedial training identified the need for closer study and briefing of instrument approaches, it is difficult to ascertain if more approach consolidation conducted prior to the incident would have prevented it.

Despite profile management and approach preparation being reinforced during the pilot’s training, the standard operating procedures outlined in the company operations manual did not give guidance to pilots as to when and how the aircraft was expected to be configured for the approach. Although an approach review was required, information pertaining to the expected cockpit and approach setup may have benefited the occurrence pilot. More generally, the absence of such guidance increases the likelihood of greater variation in how approaches are conducted.

Safety issues and actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Royal Flying Doctor Service Central Operations

Since this occurrence, the operator has implemented the following improvements:

  • amended the descent, arrival and approach procedures to include more prescriptive requirements
  • upgraded the legacy fleet to include dual global positioning system equipment with moving map and chart overlay displays to improve pilot situation awareness
  • rewritten the Training and Checking manual to include more prescriptive training
  • strengthened the Safety Management System, including the introduction of a phased implementation of a change management program
  • changed the initial pilot training, which is now conducted by their recently approved Part 141 organisation.

Findings

From the evidence available, the following findings are made with respect to flight below the minimum permitted altitude involving Pilatus PC-12, registered VH-FDJ, that occurred about 19 km north‑east of Adelaide Airport, South Australia on 18 July 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.

Contributing factors

  • The unexpected failure of the autoflight system to intercept and track the localiser resulted in the aircraft deviating from the surveyed instrument approach path and significantly increased the pilot’s workload.
  • The pilot’s focus on resolving the aircraft's lateral tracking and perceived autoflight issues during the localiser intercept decreased his attention on managing the aircraft’s approach profile. That led to the aircraft descending off-track below the minimum safe altitude.

Other factors that increased risk

  • The pilot did not initiate a missed approach despite being uncertain of the displayed navigation system information and aircraft position. This limited the opportunity for the pilot to resolve any perceived navigation issues at a safe altitude and in a more controlled environment.
  • Approach guidance in the operations manual did not include detail of the expected cockpit and approach setup preparation. That increased the risk that variation in the conduct of approaches may be introduced into operations.

Other findings

  • Detection and intervention by the air traffic controller following the off‑track descent below the minimum permitted altitude restored safe operation.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • Airservices Australia
  • Civil Aviation Safety Authority
  • FlightAware
  • the flight crew and operator.

References

Civil Aviation Authority, 2016, CAP737 – Flight-crew human factors handbook, Civil Aviation Authority, United Kingdom.

Green RG, Muir H, James M, Gradwell, D, Green RL (1996) Human Factors For Pilots, Second Edition, Ashgate, England.

Harris, D (2011) Human Performance on the Flight Deck, Ashgate, England.

Orlady H & Orlady LM (1999) Human Factors in Multi-Crew Flight Operations, Ashgate, England.

Submissions

Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to Airservices Australia, the flight crew, the operator and the Civil Aviation Safety Authority.

A submission was received from the operator. The submission was reviewed and where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2018

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2017-075
Occurrence date 18/07/2017
Location 19 km north-east of Adelaide Airport
State South Australia
Report release date 18/12/2018
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight below minimum altitude
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Pilatus Aircraft Ltd
Model PC-12/47
Registration VH-FDJ
Serial number 861
Aircraft operator Royal Flying Doctor Service of Australia Central Operations
Sector Turboprop
Operation type Medical Transport
Departure point Alice Springs, Northern Territory
Destination Adelaide, South Australia
Damage Nil

Accredited Representative – Engine failure involving an Arion Lightning aircraft, registered N273DB, New River, Arizona, United States, on 10 July 2017

Summary

On 10 July 2017, at about 1445 Coordinated Universal Time (UTC), an amateur-built Arion Lightning light sport aircraft, registered N273DB, fitted with a Jabiru 3300 engine, was substantially damaged during a forced landing following a partial loss of engine power near New River, Arizona, United States. The pilot, the sole occupant, received minor injuries.

As the accident occurred in the United States, the National Transportation Safety Board (NTSB) was responsible for investigating this occurrence. As part of its investigation, the NTSB notified the Australian Transport Safety Bureau (ATSB) as the state of manufacture of the engine. In accordance with clause 5.18 of Annex 13 to the Convention on International Civil Aviation, the ATSB appointed an accredited representative to liaise with the NTSB and initiated an investigation under the Australian Transport Safety Investigation Act 2003.

The ATSB has concluded its support of this investigation. On 9 August 2019, the NTSB released the final investigation report into this occurrence and it is available at www.ntsb.gov.

Any enquiries regarding the investigation and report should, in the first instance, be directed to the NTSB.

Occurrence summary

Investigation number AE-2017-076
Occurrence date 10/07/2017
Location New River, Arizona (17 miles north of Deer Valley Airport ((KDVT)), US
State International
Report release date 24/10/2019
Report status Final
Investigation level Defined
Investigation type External Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Engine failure or malfunction
Occurrence class Accident
Highest injury level Minor

Aircraft details

Model Lightning with Jabiru engine
Registration N273DB
Sector Piston
Operation type Private
Departure point Glendale Municipal Airport (KGEU) Arizona, USA
Destination Glendale Municipal Airport (KGEU) Arizona, USA
Damage Substantial

Collision with terrain involving Zaklad Remontow I Produkeji Spreztu Lotnicz MDM-1P FOX-P glider, VH-GPT, Lismore Airport, New South Wales, on 29 July 2017

Discontinuation notice

Report release date: 22/09/2017

Section 21 (2) of the Transport Safety Investigation Act 2003 (the Act) empowers the Australian Transport Safety Bureau (ATSB) to discontinue an investigation into a transport safety matter at any time. Section 21 (3) of the Act requires the ATSB to publish a statement setting out the reasons for discontinuing an investigation.

On 29 July 2017, the ATSB commenced an investigation into a collision with terrain involving a Zaklad Remontow I Produkeji Spreztu Lotnicz MDM-1P FOX-P glider, registered VH-GPT, at Lismore Airport, New South Wales.

The ATSB found that while conducting an aerobatic display, the glider impacted the ground heavily during the final manoeuvre. The pilot was seriously injured. Examination of the aircraft identified no mechanical issues or faults that may have contributed to the accident.

The Gliding Federation of Australia has conducted an investigation of this accident and the public report (S-1010) is availiable on their website.

The ATSB has also reviewed the safety and administrative procedures necessary to conduct air shows and found that, in this case, preparations were consistent with regulatory requirements. The ATSB investigation AO-2017-013, Mallard aircraft, Perth, January 2017 is examining a range of issues associated with air shows, including the suitability of the regulations, approval and oversight of air shows, and compliance with regulatory approvals during air shows.

In this case, the ATSB did not identify any organisational or systemic issues that contributed to the development of the accident or that might adversely affect the future safety of aviation operations. The ATSB assessed that no safety issues would be identified through further investigation. On that basis, the ATSB will discontinue this investigation.

Occurrence summary

Investigation number AO-2017-077
Occurrence date 29/07/2017
Location Lismore Airport
State New South Wales
Report release date 22/09/2017
Report status Discontinued
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Serious

Aircraft details

Model Zaklad Remontow I Produkeji Sprzetu, MDM-1P FOX-P
Registration VH-GPT
Serial number 232
Aircraft operator Private
Operation type Gliding
Departure point Lismore, New South Wales
Destination Lismore, New South Wales
Damage Substantial

Derailment of freight train 1501S, near Dry Creek, South Australia, on 28 July 2017

Final report

Report release date: 31/10/2018

Safety summary

What happened

At about 0617 on 28 July 2017, a Bowmans Intermodal containerised ore train (1501S) travelling empty from Port Flat, South Australia (SA) stopped at Dry Creek South in SA. The driver felt the performance of the train ‘very sluggish’, as it was not rolling as it had prior to rounding a curve on the approach to Dry Creek South. The train crew notified the Australian Rail Track Corporation (ATRC) network control officer at Mile End, SA of their situation and that they intended to inspect their train. A short time later, the train crew confirmed to the network control officer that the last three wagons from 1501S had derailed. The train crew were uninjured. However, there was substantial damage to the wagons, track and signalling infrastructure.

What the ATSB found

The ATSB found a vertical split head defect had developed undetected from imperfections introduced during the manufacture of the rail 90 years ago. The defect propagated vertically and longitudinally, roughly through the centre line of the lower leg rail in the curve approaching Dry Creek South.

The passage of a previous train (1122) over this section of track caused an initial rail break, affecting the integrity of the rail and electrical continuity of the associated track circuit, which prevented a signal from clearing for the next train (1501S). The network control officer authorised the driver to pass the signal at stop, with the condition that the train travel at low speed.

However, the rail break was not visually obvious to the train crew as the locomotive rounded the curve. As the rear of that train passed over the break, a 2 m section of rail fragmented causing the last three wagons to derail.

Detailed (ultrasonic) inspection of the track about one month prior to the occurrence recorded a sustained loss of back wall echo at the derailment location, automatically marking the rail with a spray of paint. However, the ultrasonic inspection operator attributed the recorded event to the poor surface condition of the railhead, which is a common condition that can inhibit the testing. There was no retesting initiated or surface condition report lodged in response to the recorded event. The absence of any follow-up missed an opportunity to identify the presence of the vertical split head defect prior to the rail fracture and the subsequent derailment of 1501S.

What's been done as a result

Following the incident, Speno implemented a review of testing techniques used by operators where poor surface condition exists and the procedures for reporting and testing of rail affected by surface condition.

The Australian Rail Track Corporation reaffirmed the adequacy of the Track and Civil Code of Practice for ultrasonic inspections and the reporting requirements in accordance with contractual arrangements with the ultrasonic inspection operator. The rail in the Dry Creek area is programmed for replacement during 2018 as part of the Adelaide to Tarcoola Re-Railing Project.

Safety message

Defects can develop in rails (and welds) due to a wide range of reasons. Early detection and treatment of a defect that could cause a fracture of the rail is of major importance. While poor surface condition of the railhead is a known limit to the effectiveness of ultrasonic testing, its presence can mask internal track defects, particularly when the condition exists over an extended area. If an inspection cannot test or can only partly test rails, maintenance personnel must report the shortfall to highlight operational risk and the requirement for a timely supplementary examination.

Fractured rail section in lower rail of curve

Fractured rail section in lower rail of curve. Source:  ATSB

Source:  ATSB


The occurrence

At about 0145 on the 28 July 2017, a Bowmans Rail freight train (1501S) was prepared for departure from Port Flat near Adelaide, South Australia (Figure 1). Train 1501S was an empty containerised ore service comprised of two locomotives (GL108 leading, CM3308 trailing) and 56 wagons. The train was 802 m long, with a trailing mass of 1,283 t and crewed by two drivers. The train was to travel via Dry Creek in South Australia to the Bemax Siding located between Thackaringa and Kanandah in New South Wales.

At about 0548, the driver of 1501S contacted the Australian Rail Track Corporation (ARTC) network control officer (NCO) located at Mile End in South Australia to advise that they were ready to depart Port Flat. The NCO notified the driver that they would travel under signal indication up to Signal 1 at Dry Creek, where a Train Authority[1] would be required for train 1501S to proceed. The NCO was unable to clear signal 1 to a proceed indication,[2] as a track circuit[3] had remained occupied following the passage of the previous train (1122) about 30 minutes earlier.

Figure 1: Location of the derailment of Train 1501S in South Australia

Figure 1: Location of the derailment of Train 1501S in South Australia. Source: Geoscience Australia annotated by ATSB

Source: Geoscience Australia annotated by ATSB

At about 0608, the train crew stopped train 1501S at signal 1, and the NCO issued the train authority for the crew to pass the signal at stop. The NCO included instructions for the train crew to proceed at low speed and stop at the points[4] to ensure they were set correctly for the route to the next fixed signal[5] (signal 5). After confirming the content of the train authority with the NCO, the driver passed signal 1 and continued toward Dry Creek South, controlling train 1501S to maintain a speed below 25 km/h.

The driver recalled that when travelling about half way around the curve between signals 1 and 5 he felt the lead locomotive pass over a dip in the left (lower leg) rail. A short time later, train performance ‘felt very sluggish’ and it was not running as it was prior to the curve. At the time, the lead locomotive (GL108) was travelling at about 17 km/h. At about 0617, the driver contacted the NCO, and advised that train 1501S had stopped at Dry Creek South and that they would inspect the train.

At about 0626, an ARTC signal maintainer arrived onsite to investigate the cause of an earlier reported fault; that is, signal 1 not clearing. Shortly after, the signal maintainer contacted the NCO advising that the rear of train 1501S had derailed and there was substantial damage to the wagons, track, location case[6] and other signalling infrastructure (Figure 2).

Figure 2: Derailed rear three wagons of 1501S and damaged signal 5 location case

Figure 2: Derailed rear three wagons of 1501S and damaged signal 5 location case. Source: ATSB

Source: ATSB

At about 0627, the driver of train 1501S contacted the NCO confirming that the last three wagons (CQYY 3264-G, CQYY 3261-C and CQYY 3265-P) had derailed. The wagons had travelled about 285 m in a derailed state before train 1501S stopped.

Site inspection

An inspection of the track identified a 2 m section of rail had fractured, on the lower leg of the left curve (Figure 3).

Figure 3: Fractured section of rail

Figure 3: Fractured section of rail. Source:  ATSB

Source: ATSB

The railhead had split vertically and longitudinally, roughly through the centre line of the rail in the affected section. The split propagated through to the head/web transition region and outward through the railhead toward the gauge side of the rail, separating the head from the web[7] (Figure 4).

The web had also fractured at several points through the affected section. These breaks were predominately vertical through the web, and transverse in the foot of the rail. The breaks through the web were due to overstress, which probably occurred during the passage of the previous train 1122, and the subsequent passage of 1501S that derailed.

Figure 4: Vertical split head section

Figure 4: Vertical split head section. Source:  ATSB

Source: ATSB

Passing signal 1 at stop

The ARTC Code of Practice, Volume 3 (CoP) defines the operations and safe working rules for managing train movement[8] through the Dry Creek area. Before authorising the crew of a train to pass a signal at stop, the CoP required the NCO, and train crew, to assess the situation including:

  • why the signal is at stop
  • if the section is clear or occupied
  • if the track is safe or unsafe
  • the conditions to be included in the Train Authority to authorise the train to pass the signal at stop.

Track circuits in the Dry Creek area used the rails and other signalling equipment as conductors to form an electric circuit. The presence of a train or other rollingstock, or a break in the electrical continuity of the circuit, will cause the track circuit to signal an occupancy.

In this case, the signal was at stop due to an indication the track section remained occupied following the movement of the previous train (1122). A track section might indicate as occupied due to a number of reasons, such as an obstruction, faulty equipment, broken electrical connections, or as in this case, a broken rail.

When travelling on a track section indicated as occupied, there is an increased risk that the train may encounter an obstruction, points incorrectly set for the intended route, or other equipment not operating as expected (for example, level crossings). Consequently, when authorising a train to pass the signal at stop, an NCO should apply conditions to ensure appropriate management of these risks.

Prior to authorising the train crew to pass signal 1, the NCO communicated to the train crew that a track circuit in the route was indicating an occupancy, preventing the signal from clearing. There was no further discussion related to the safety of the track. However, the NCO issued conditions in the train authority for the driver to proceed past signal 1 at low speed and for the train to stop at points to ensure they were set correctly for the intended route. The CoP defined low speed as a speed which will enable a train movement to be stopped within half the distance that the track is seen to be clear ahead, but does not exceed 25 km/h.

Typically, a simple rail break would not result in a derailment, especially if a train is travelling at low speed. This is because, as in this case, the CoP also required a train crew to maintain vigilance by being alert, observing the track (including rails) in the direction of the movement, and being prepared to stop or reduce train speed if required.

Train 1501S passed signal 1 about an hour before sunrise. The driver continued at speeds below 25 km/h, travelling approximately 1,290 m toward Dry Creek South before stopping. Although the driver reported to the NCO that the locomotive dipped to the left when rounding the curve, the train crew did not report observing any significant anomaly with the track and were likely unaware that a rail had broken.

The locomotives and all wagons with the exception of the last three remained on the track. It is likely the rail disintegrated during the passage of one of the last two wagons (CQYY 3261-C or CQYY 3265-P) over the failed section of track. The derailment of the last two wagons likely pulled the rear bogie of the third to last wagon, CQYY 3264-G from the track. The rear of train 1501S travelled about 285 m from the point of derailment (break in the rail) before stopping.

Track inspection arrangements

The ARTC Track and Civil Code of Practice – Rail, defines the guidelines for the scheduled inspection the assessment of rail and rail wear. The scheduled inspections included:

  • A patrol inspection of the rail for visible defects and conditions (i.e. indications of a defect) that may affect the integrity of the track structure, including the following:
    • broken rails and rail welds
    • rail and rail weld deformations and discontinuities
    • wheel burns
    • damage to rail surface or section
    • unusual patterns of gauge face contact
    • unusual vehicle tracking patterns
    • rail corrugation
    • rail crippling
    • other obvious indications of defects (e.g. bleeding).[9]

The patrol inspections were typically carried out from an on-rail vehicle travelling at a speed consistent with the inspection or by walking. Where track circuits were installed, these could also be employed as an additional method to detect rail failures (such as a break). Patrols conducted two type of inspections:

  • A general inspection to visually inspect new welds or where the response following detection of a rail or weld defect is to ‘observe’.
  • A detailed inspection, carried out through continuous or manual ultrasonic rail flaw detection.
    • Continuous and manual ultrasonic rail flaw detection involved passing sound waves into the rail and monitoring the echo returned by the sound waves reflecting off internal and external surfaces (reflectors). Defects within the rail create reflectors that return echo patterns depending on their type, location and size. Examination of the reflectors enables a skilled operator to deduce the existence, type and size of a suspected rail defect.

The ARTC Civil Technical Maintenance Plan ETE-00-03 sets out the routine inspection tasks and minimum inspection frequency for the track and civil infrastructure (Table 1).

Table 1: Summary from Technical Maintenance Plan – Track System

Type of inspectionInfrastructure elementDescriptionMinimum FrequencyConducted by

Track patrol inspection

(By road /rail vehicle or by walking)

Rails and JointsIncludes: Rail; New Welds; Mechanical and insulated Joints; Rail wear; Lubrication1 Patrol / 7 days
(1 day latitude)
Track inspector
Rail detailed inspectionRail - internalContinuous ultrasonic rail flaw inspection or manual hand-held inspection where continuous inspection is not effectiveAt least every 15 MGT[10]-

Source: ARTC modified by ATSB

Track Patrol inspection

The ARTC standard for Track Patrol, Front of Train, General and Detailed Inspections specifies the scope and methodology for the performance of this inspection. The standard recognises the track patrol is principally:

A visual inspection intended to detect obvious, abnormal conditions. It is unlikely that hidden failures or conditions that don’t have a significant visual impact will be detected by Track Patrol which is typically performed from a hi-rail vehicle at moderate speed. Other scheduled (and ad-hoc) general and detailed inspections focus on specific components or conditions and are intended to detect these less obvious defects.

On 27 July 2017, the day preceding the derailment of 1501S, the ARTC track inspector completed a track patrol inspection for the section of rail between the Dry Creek Triangle[11] and Pelican Point. The track inspector did not record observing any anomaly in the rail condition through the area where the derailment occurred.

Continuous ultrasonic rail flaw inspections

ATRC’s technical maintenance plan specified the minimum frequency for a detailed inspection (ultrasonic rail flaw inspection) was at least every 15 MGT. Although the track section between the Dry Creek Triangle and Pelican Point carried around 7 – 10 MGT per annum, ARTC scheduled the detailed inspections yearly.

ARTC undertook the detailed inspections in the Dry Creek Triangle to Pelican Point section through a contractual arrangement with Speno Rail Maintenance Australia (Speno). The Speno Site Safety, Environmental & Quality Management Plan ARTC - Rail Flaw Detection, detailed the specific requirements for Speno accessing the rail network and the rail testing process undertaken.

The rail testing process typically involved the operation of two on-track vehicles. For this type of operation, a main test vehicle (Figure 5) would conduct continuous testing where the ultrasonic operator would interpret, mark and log ultrasonic events displayed on the test vehicles display monitors. Automatic paint guns sprayed a white paint mark on the gauge side, rail web and foot of each rail when the system detected the presence of a defined event.

Following the identification of an event, the operator in the main test vehicle relayed information to a following vehicle, where an operator in that vehicle was responsible for manual ultrasonic testing to localise, identify, size and assess the detected flaw in accordance with the relevant ARTC standards.

The ARTC Manual for Non-Destructive Testing of Rail, ETN-01-04 included specifications for the ultrasonic test equipment and the types and sizes of rail flaws for detection. The manual required the ultrasonic operators to use a range of probes when inspecting the rail and welds for cracks and similar discontinuities. The main test vehicle used in testing the rail in the Dry Creek area towed the roller search unit equipped with an array of 0°, 38° and 70° probes (Figure 5). The arrangement of the probes enabled continuous inspection of each rail leg for defects in various orientations.

Figure 5: FL-18 (RFAS-2100) rail analysis system (main test vehicle)

Figure 5: FL-18 (RFAS-2100) rail analysis system (main test vehicle). Source:  Speno Rail Maintenance Australia, annotated by ATSB

The 0° probe examined the full rail depth, including welds (Figure 6). Defects located by this probe include bolt hole cracks and longitudinal defects of a horizontal nature in the railhead, web and foot. However, vertical defects are more difficult to detect by continuous ultrasonic testing of rail, since the vertical surface of the defect is less likely to provide a clear reflection from any probe.

While the presence of a vertical split head defect may not display as a distinctive signature in the reflected signal on the operators screen, there are signature patterns that may indicate a potential issue. A vertical defect in the railhead may present as a loss of back wall echo (LBWE), where the signal from the 0o probe is deflected, thereby causing the reflected signal from the base of the rail (foot) to drop below a pre-defined level.

Figure 6: Area 0° probe coverage

Figure 6: Area 0 degrees probe coverage. Source:  Australian Rail Track Corporation

Source:  Australian Rail Track Corporation

A loss of signal from the bottom of the rail, over any length greater than 4 mm is displayed to the operator in the raw data. A loss of signal over 50 mm will activate an audible signal to the operator that has a unique tone dependent on the respective rail and display the LBWE as a length value to the operator. The pulse echo reliant transducers also activate the automatic paint guns spraying location marks on the rail web. Any ultrasonic shielding (LBWE) or anomalous indication should trigger a localised visual inspection and manual ultrasonic scanning from other faces of the rail to investigate.

The ARTC standard, Non-Destructive Testing of Rail ETE-01-03 detailed the response actions and timeframe to levels of shielding and testability of rail (Table 2).

Table 2: Summary from standard, non-destructive testing of rail

Shielding levelPurpose of assessmentDefinitionResponse time(s)Action(s)
MinorRequire test car to re-test at low speed

Any of the following testing at normal speed

  • Vehicle had to reduce speed
  • LBWE greater than 50 mm
  • More than one LBWE per m
  • Line difficult to test

Immediately


7 days

Stop, examine rail to identify cause of loss of detection

Re-test at 5 km/h

Test car shall report shielding

ModerateReport early stages for remediation or remediation planning

Any of the following testing at reduced speed

  • LBWE between 50 and 200 mm
  • If rail difficult to test
3 days

Test car shall report shielding

Rectification within timeframes specified in Corridor Management Plan

MajorRequire hand testing if test car cannot test

Any of the following testing at reduced speed

  • LBWE greater than 200 mm
  • More than one LBWE per m
  • One or more probes giving inconsistent results

7 days


1 day

Test affected rail by hand or apply Track Speed Restriction as required

Test car shall report shielding

Source: ARTC modified by ATSB

The continuous ultrasonic inspection was undertaken on 26 June 2017, about one month prior to the derailment of train 1501S. There was no ultrasonic reflector indicating a vertical split head defect. However, there were occasions of intermittent LBWE and a prolonged period of LBWE over about 2 m that coincided with the derailment location (Figure 7). The inspection also indicated the presence of spurious reflectors from the 70° shear wave transducers. These reflectors likely emanated from the poor rail surface condition that often occurs when the roller search unit is having difficulty maintaining continuity with the rail.

Figure 7: Ultrasonic signatures at derailment location on 26 June 2017

Figure 7: Ultrasonic signatures at derailment location on 26 June 2017. Source: Speno Maintenance Australia, annotated by ATSB

Source: Speno Maintenance Australia, annotated by ATSB

Following the derailment, Speno reviewed replays and examined the ultrasonic signatures from other track structures (insulated joints and boltholes) taken in the area and confirmed the ultrasonic testing system in the main test vehicle was operating within normal parameters at that time.

Examination of the replays also suggested that the operator was having trouble (on occasion) in maintaining continuity of the roller search unit with the rail surface during the run. To compensate, the operator of the test vehicle was undertaking the testing at a reduced speed of 5 km/h, as specified in the response actions of the ARTC procedure.

The Speno rail analysis unit was equipped with audible alarms and paint spray guns that flagged the LBWE event as an exceedance and marked the rail during the ultrasonic inspection of the 26 June 2017 (Figure 8).

The prolonged LBWE event and continued difficulty experienced in testing should have triggered the next level of response action. If rail could not be tested or only partly tested, due to ultrasonic shielding, ARTC required the operator to test the affected area by hand or to forward a Rail Surface Condition Report detailing the circumstances that impeded the testing. Neither a response action nor a condition report was initiated in this case.

Figure 8: Failed section of railhead showing markings from ultrasonic car testing

Figure 8: Failed section of railhead showing markings from ultrasonic car testing. Source: ATSB and ARTC (inset photograph)

Source: Speno Maintenance Australia, annotated by ATSB

The previous ultrasonic test of rail in the Dry Creek area occurred in May of 2016. This test also recorded an intermittent LBWE in the same vicinity. Prolonged periods of LBWE also occurred on the opposite rail (Figure 9) illustrated at the 0.226 km mark. Similarly, there was also no record of retesting or the lodgement of a surface condition report. It is likely that the operator on this occasion also assessed the spurious reflectors and LBWE were, in the absence of defined defect signatures, due to the poor surface condition of the railhead.

Figure 9: Ultrasonic signatures at 0.226 km point 4 May 2016

Figure 9: Ultrasonic signatures at 0.226 km point 4 May 2016. Source: Speno Maintenance Australia, annotated by ATSB

Source: Speno Maintenance Australia, annotated by ATSB

__________

  1. An instruction in the prescribed format issued by the train controller in connection with the movement of a train.
  2. Any signal indication other than stop.
  3. An electric circuit that uses the rails of a railway as conductors such that a train electrically connects them via its axles. The absence or presence of this rail-to-rail connection indicates the absence or presence of a train or item of rollingstock.
  4. A set of points permits rail traffic to change from one track to another. Points are normally referred to as left or right hand denoting the turnout direction as viewed from the toe end.
  5. A manually or power operated signal which is permanently located near the line.
  6. Signalling lineside apparatus housings at a particular site and the equipment contained therein.
  7. That part of the rail between the head and the flange (foot).
  8. The operation on rail of a train or other track vehicle or machine.
  9. Discolouration on the web due to the movement of oxides to the surface.
  10. Million Gross Tonnes.
  11. Dry Creek Triangle includes the track section between signal 1 and signal 5.

Safety analysis

The rail installed in the lower leg of the curve at the Dry Creek North Fork displayed the manufacturer brand, AS BHP Co Ltd 1X27 100LBS OH. The branding indicates the manufacture date was in 1927, from an open-hearth (OH) furnace process. Older rails, produced by means of OH furnaces and cast into ingots, generally exhibited higher levels of impurities than rails produced through the current continuous casting process.[12]

The rail at the derailment site was installed in 1999. The running surface of the rail at the derailment location and in the curve exhibited rolling contact fatigue (RCF) defects that developed from shear stresses at the rail-wheel interface. The presence of RCF defects such as plastic flow, flaking and minor spalling, can mask the signal during ultrasonic inspection and hence prevent the detection of larger and deeper defects that may be present within the railhead.[13]

On-site examination of the section of rail showed evidence of an internal seam extending vertically within the centreline of the railhead. The seam surfaces were heavily corroded and punctuated by an elongated band of inclusions and oxidation located at a depth of around 10 mm from the running surface of the railhead (Figure 10). The general appearance and orientation of the inclusion banding indicated that it was pre-existing and very likely to have been produced when the rail was cast at the time of manufacture. Fatigue cracking had developed from the inclusion bands and had then propagated toward the railhead-running surface and the web transition region, creating a ‘vertical split head’. Typically, longitudinal crack propagation is influenced by a combination of increasing axle loads, wheel impacts or eccentric loading on a railhead exhibiting a flattened profile.

Figure 10: Railhead section detailing interior seam of inclusions/imperfections

Figure 10: Railhead section detailing interior seam of inclusions/imperfections. Source: ATSB

Source: ATSB

The vertical split head in this instance propagated undetected into a critical defect of around 2 m in length. The defect exhibited the typical visual indicators of well-developed dark oxide streaking on the centreline of the running surface and oxide streaks (bleeding) on the fillet area of the rail web under the defect (Figure 11). The forces exerted by the passage of train 1501S across the area of rail containing the vertical split defect (and broken rail) resulted in the fragmentation of that section of rail. The disruption of the rail running surface then led to the derailment of the last three wagons of train 1501S.

Track inspection

As neither the scheduled track patrol nor ultrasonic inspection identified the presence of a defect, it cannot be determined when the vertical split defect first propagated towards a critical size. The yearly ultrasonic inspection is heavily reliant on the ability of the individual operator to detect and interpret anomalies in the rail infrastructure (or displayed ultrasonic signatures) that signal the presence of a potential defect.

Figure 11: Failed section of railhead

Figure 11: Failed section of railhead. Source: ATSB

Source: ATSB

The continuous inspection of rail infrastructure by track patrol or ultrasonic test vehicles typically involves the operator undertaking repetitive tasks in scanning the track structures (or visual display screens) for anomalies while operating a vehicle or other on-board equipment over long sections of track. Track patrols undertaken from road-rail vehicles target the identification of abnormal conditions that may affect the integrity of the infrastructure or operation of rollingstock. Defects that do not have a significant visual impact may be overlooked, increasing the reliance on the detailed inspections to detect hidden conditions.

The Australian Rail Track Corporation (ARTC) also recognised that the non-destructive testing used in undertaking the detailed inspections did not assure detection of all defects due to limitations of existing ultrasonic techniques.

To minimise the risk of a missed defect, ARTC required the ultrasonic testing process, and in particular the conditions in the testing vehicle, be optimised to facilitate the concentration of the operator on the data being analysed. This included:

  • the judicious use of post analysis facilities of recorded data
  • in-car working conditions and temperature
  • computer screens that are adequately protected from sun glare
  • monitoring that the speed of the car is compatible with the ability to analyse data presented
  • safe working practices are adequately catered for outside the time allowed for test analysis
  • fatigue management of operators (consideration of rotation of operators with hand testers)
  • undue pressure on time allowed in section
  • peer development and regular training in compliance with this document
  • monitoring of operators’ performance in terms of percentage of defect identified.

On the 26 June 2017, Speno Rail Maintenance Australia (Speno) commenced the ultrasonic inspection of track at Pelican Point and then proceeded towards Dry Creek. Speno identified that the inspection run at Dry Creek through the area of the derailment would therefore have occurred at about 1645, toward the end of the operators shift. However, there was no further evidence to suggest that fatigue contributed to a failure to detect a rail defect.

The rail in the area of the derailment and a number of other areas along this section of track was in relatively poor condition and exhibited heavily flowed head[14] with severe flaking[15] on the rail surface. The condition of the railhead probably resulted in the failure of the roller search unit to maintain effective contact with the rail surface during the run, either producing spurious reflectors or inhibiting transmission of ultrasonic signals from a defect.

The operator did not follow-up the loss of back wall echo (LBWE) trace and alarm in the area of the derailment by triggering a localised ground inspection or forwarding a rail surface condition report to ARTC.

The generally poor condition of the track in the area of the derailment meant the operator received many spurious ultrasonic reflectors and alarms while traversing that track section. It is likely that the operator’s assessment of the importance of the indications decreased relative to the rail condition, track category and test frequency. Consequently, the operator attributed the LBWE indications to surface condition, rather than the presence of a defect.[16]

__________

  1. Vertical split head defects – some insights into their development and growth, Stephen Marich and Malcom Kerr, RTSA Conference on Railway Engineering, Darwin 20-30 June 2004, p 21.3
  2. Rail defect handbook RC2400, Australian Rail Track Corporation Issue A, Revision 0, March 2006, p29
  3. Rolling out of the metal of the head towards the sides without a breaking down of the underside of the head.
  4. A condition that occurs on the running surface appearing as a mosaic like pattern of small cracks.
  5. Speno Broken rail report CTT 2014-016, 8 August 2017.

Findings

From the evidence available, the following findings are made with respect to the derailment of freight train 1501S near Dry Creek on the 28 July 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.

Contributing factors

  • An undetected defect resulted in the formation of a longitudinal fracture within the railhead that propagated both longitudinally and vertically (parallel to the side of the head).
  • The forces exerted by the passage of train 1501S across the area of rail containing the vertical split defect (and broken rail) resulted in the fragmentation of a 2 m section of rail. The disruption of the rail running surface resulted in the derailment of the last three wagons of train 1501S.

Other factors that increased risk

  • The operator undertaking ultrasonic testing of rail at Dry Creek North Fork on 26 June 2017 assumed the reflectors recorded resulted from the poor surface condition of the railhead and did not follow-up the loss of back wall echo indication that occurred at the location of the rail break.

Other findings

  • The passage of a previous train (1122) across the section of rail containing the vertical split defect likely caused the rail to break, further reduced the integrity of the track to support the passage of rollingstock at this location.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence

Proactive safety action taken by Speno Rail Maintenance Australia

Following the incident, Speno Rail Maintenance Australia investigated the broken rail occurrence and implemented a review of testing techniques used by operators in areas where poor surface condition exists and the implementation of procedures for reporting and testing of rail affected by surface condition.

Proactive safety action taken by Australian Rail Track Corporation

Following the incident, the Australian Rail Track Corporation (ARTC) addressed with Speno the reporting arrangements required in accordance with the contract between the two parties. Additionally ARTC reaffirmed the adequacy of the Track and Civil Code of Practice in relation to ultrasonic inspections.

The rail in the Dry Creek area is programmed for replacement during 2018 as part to the Adelaide to Tarcoola Re-Railing Project.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • Australian Rail Track Corporation
  • Bowmans Rail
  • Speno Rail Maintenance Australia

References

Track and Civil Code of Practice, Rail, Section 1, Version 3.3, 22 July 2016, Australian Rail Track Corporation

Code of Practice for the Defined Interstate Rail Network, Volume 4, Operations and Safe working , Part 1: Rules, DOTARS Version 2: May 2002, ARTC Version 2.2: 04 October 2015, Department of Transport and Regional Services

Engineering (Track & Civil) Manual, Manual for Non-Destructive Testing of Rail, ETN-01-04, Version 1.3 07 July 2009, Australian Rail Track Corporation

Non-Destructive Testing of Rail (for Internal & Surface Defects), ETE-01-03, Version 1.6, 6 October 2016, Australian Rail Track Corporation

Rail Defects Handbook, Some Rail Defects, their Characteristics, Causes and Control, RC 2400 Issue A, Revision 0, March 2006, Australian Rail Track Corporation, pp. 48-54

Rail Defect Manual, Sperry Products Inc., Hobroken. N.J. 1942

Site Safety, Environmental & Quality Management Plan, ARTC – Rail Flaw Detection, Version 3 17/02/2015, Speno Rail Maintenance Australia

Site Safety, Environmental & Quality Management Plan ARTC - Rail Flaw Detection, Version 3 17.02.2015, Speno Rail Maintenance Australia

Track Patrol, Front of Train, General and Detailed Inspections, ETE-00-02, Version 1.7 28 Jun 16, Australian Rail Track Corporation

Vertical split head defects – some insights into their development and growth, Stephen Marich and Malcom Kerr, RTSA Conference on Railway Engineering, Darwin 20-30 June 2004, p 21.3

Submissions

Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the Australian Rail Track Corporation, Bowmans Intermodal, Speno Rail Maintenance Australia and the Office of the National Rail Safety Regulator.

Submissions were received from the Australian Rail Track Corporation, Speno Rail Maintenance Australia and the Office of the National Rail Safety Regulator. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2018

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number RO-2017-008
Occurrence date 28/07/2017
Location Dry Creek South
State South Australia
Report release date 31/10/2018
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Rail
Rail occurrence category Derailment
Occurrence class Incident
Highest injury level None

Train details

Train operator Bowman Rail
Train number 1501S
Type of operation Freight train
Departure point Pelican Point, South Australia
Destination Bemax Siding, New South Wales
Train damage Substantial

Level crossing collision between a car and XPT NT35, Kyogle, New South Wales, on 14 June 2017

Discontinuation notice

Report release date: 15/02/2019

Section 21 (2) of the Transport Safety Investigation Act 2003 (TSI Act) empowers the Australian Transport Safety Bureau (ATSB) to discontinue an investigation into a transport safety matter at any time. Section 21 (3) of the TSI Act requires the ATSB to publish a statement setting out the reasons for discontinuing an investigation.

On 14 June 2017, the ATSB commenced an investigation into a level crossing collision between a car and XPT NT32, Kyogle, New South Wales, Australia.

At approximately 0810 (AEST) on 14 June 2017, the driver of a white Holden Commodore was driving across the Andrew Street level crossing at Kyogle.  At the same time, XPT NT32 travelling from Brisbane to Sydney was approaching the level crossing. The train struck the motor vehicle and as a result of the collision, the driver of the car suffered fatal injuries.

ATSB’s preliminary evidence collection revealed:

  • The passive level crossing approach signage was to standard.
  • The sighting distances from both sides of the level crossing were unobstructed and provided ample time for safe crossing.
  • There was no evidence of the level crossing being poorly maintained.
  • There were no mechanical issues identified with the train.
  • There were no issues identified with the train driver.
  • The driver of the car was walking their pet dog beside the vehicle over the level crossing.

Based on this information, it is likely the driver of the car did not see the train approaching and did not abide by the passive level crossing warning signs. The ATSB considered it was very unlikely that further investigation would identify any systemic safety issues. Consequently, the ATSB has discontinued this investigation.

Occurrence summary

Investigation number RO-2017-004
Occurrence date 14/07/2017
Location Kyogle
State New South Wales
Report release date 15/02/2019
Report status Discontinued
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Rail
Rail occurrence category Level Crossing
Occurrence class Accident
Highest injury level Fatal

Train details

Train operator NSW Trains
Train number NT35
Type of operation XPT Passenger service
Departure point Brisbane, Queensland
Destination Sydney, New South Wales
Train damage Minor

Derailment of coal train 9869, 8 km west of Oakey, Queensland, on 21 July 2017

Final report

Report release date: 26/06/2019

Safety summary

What happened

On 21 July 2017, a loaded coal train derailed at a level crossing on the Western Line between Oakey and Jondaryan, Queensland. The hauling locomotives and 18 wagons came off the track, destroying about 300 m of rail infrastructure.

It is very likely that the underframe of a low-clearance heavy road vehicle collided with the railway infrastructure as it traversed the level crossing soon before the coal train reached the crossing. The impact with railway infrastructure resulted in the lateral displacement of rail lines, which consequently derailed the coal train.

What the ATSB found

The rail infrastructure manager’s monitoring and inspection process at the Dunkeld Access Road level crossing did not ensure the approach roads within the rail corridor and the crossing surface were maintained within safe operating limits throughout its lifecycle. As a result, the elevated gravel-based level crossing road and crossing surface deteriorated to a point where the underframe of a low-clearance heavy road vehicle collided with the exposed head of each rail as it traversed the crossing.

The driver of the heavy road vehicle did not report the collision with rail infrastructure to the asset owner (Queensland Rail) or the local police in accordance with the Queensland Government road transport guidelines. Therefore, the relevant authorities were not in a position to contact the driver of the train before reaching the level crossing.

At the time of the derailment, there was no interface agreement between the rail infrastructure manager and a responsible road authority.

What's been done as a result?

Following the derailment, Queensland Rail (QR) repaired the level crossing and installed a sealed asphalt surface on both sides of the crossing to mitigate the risk of erosion and deterioration. QR also advised that it had taken or was undertaking a series of actions to improve its inspection processes of level crossings to ensure that more focus is placed on inspecting the condition of the approach roads at the crossings. In addition, QR is reviewing its safety standards and relevant documentation in relation to identified defects at level crossings and how the defects are recorded and managed.

QR also advised it had a state-wide audit program in place to assess the current safety status of all private crossings, and upgrade them to the QR standard and/or seek to enter interface agreements.

Safety message

Rail infrastructure managers, who are responsible for the management of the rail corridor, need to ensure that approach roads and the crossing surface at level crossings are subject to regular and effective inspection and monitoring processes. This is particularly relevant for level crossings with gravel-based road surfaces and inclined approach roads.

If rail infrastructure is damaged due to a road accident, it is vitally important that the driver responsible report the matter to the local police or the asset owner as soon as possible.


The occurrence

At about 1550 Eastern Standard Time[1] on 21 July 2017, loaded Aurizon coal train 9869, operating on the Queensland Rail network, departed from the Jondaryan Coal Siding for Fisherman Islands, Queensland (Figure 1). The train was crewed by two drivers, and the consist included two locomotives and 41 wagons.

Figure 1: Jondaryan Coal Siding to Fisherman Islands rail route

Figure 1: Jondaryan Coal Siding to Fisherman Islands rail route. The image shows the projected journey of train 9869 from Jondaryan Coal Siding to Fisherman Islands. 
Source: Queensland Rail (QR)

The image shows the projected journey of train 9869 from Jondaryan Coal Siding to Fisherman Islands. Source: Queensland Rail (QR)

At about 1534, prior to the departure of the train, a low-clearance heavy road vehicle (prime mover and low-loader) was travelling west along the Warrego Highway between Oakey and Jondaryan. The driver of the heavy road vehicle made a right turn off the highway on to Dunkeld Access Road and passed over level crossing ID 2309, which provided a connection from the highway to McKenzie Road (Figure 2). The level crossing was located at the 38.620 km[2] mark on the Western Line.

Figure 2: Travel direction of the heavy road vehicle over level crossing ID 2309

Figure 2: Travel direction of the heavy road vehicle over level crossing ID 2309. The image depicts the movement of the heavy road vehicle (white arrows) and the passageway of train 9869 (white solid line) in relation to the level crossing. 
Source: Google Earth - annotated by Australian Transport Safety Bureau (ATSB)

The image depicts the movement of the heavy road vehicle (white arrows) and the passageway of train 9869 (white solid line) in relation to the level crossing. Source: Google Earth - annotated by Australian Transport Safety Bureau (ATSB)

A member of the public saw the heavy road vehicle come to a sudden stop as it passed over the level crossing. According to the witness, the driver left the driving cab of the prime mover and inspected under the low-loader while it was stopped on the level crossing. The heavy road vehicle then continued on its journey, proceeding east along McKenzie Road.

At about 1557, as train 9869 approached level crossing ID 2309, the driver operating the train detected something on the track ahead. Initially, he thought a bird or small animal on the rails had distorted the appearance of the track, which is a common sight in this region. However, as the train neared the level crossing, the driver noticed a ‘kink’ in both rails. At that point, the speed of the train was 55 km/h, which was within the relevant limit for that section of track.

The driver reported that, as soon as he noticed the kink in the rails, he attempted to stop the train. At about 1558, the data logger on the locomotive recorded a full service brake application, which was initiated by the train driver to control the train to stop. The driver stated that the lead locomotive shuddered as it passed through the level crossing, and through the side mirrors he observed a number of wagons derail as the train slowed.

There were no injuries to the train crew or members of the public. A visual inspection of the train identified both locomotives and 18 coal wagons had derailed. There was also damage to about 300 m of rail infrastructure (Figure 3).

Figure 3: Derailed coal wagons of train 9869

Figure 3: Derailed coal wagons of train 9869. The image shows derailed coal wagons of train 9869 – all wagons in the scene were in a derailed state. 
Source: ATSB

The image shows derailed coal wagons of train 9869 – all wagons in the scene were in a derailed state.

Source: ATSB

__________

  1. Eastern Standard Time (EST): Coordinated Universal Time (UTC) + 10 hours.
  2. Kilometres west of Toowoomba.

Context

Level crossing information

History and location of level crossing ID 2309

In 1948, the Commissioner for Railways in Queensland, at the request of a local property owner, closed the occupation level crossing at the 124 miles 52 chains Western Line and relocated it to the 124 miles 70 chains, opposite the property owner’s farm. The relocation of the crossing provided the property owner with ready access to the Warrego Highway. Over time, the property was subdivided into smaller farms, which border the northern side of McKenzie Road and the Western Line.

Level crossing ID 2309 is currently located midway between Oakey and Jondaryan on the Western Line. Although the location of the level crossing has not changed in 70 years, under the metric system, its position is at the 38.620 km mark Western Line. It was categorised as a private (occupation) level crossing.[3] At the time of the derailment, the crossing was used by the general public, including heavy road vehicles.

Queensland Rail (QR) has been the sole contributor to maintenance for both the level crossing and the approach roads within the rail corridor[4] since the relocation in 1948.

Maintenance requirements for private level crossings

QR’s Level Crossing Safety Standard MD-10-115 stated that QR was responsible for audits, inspections, maintenance and testing at private level crossings. The maintenance responsibilities included (in part):

• erecting and maintaining all signs immediately adjacent to the tracks as set out in the level crossing agreement, deed or license (if applicable);

• maintaining the road surface within the rail corridor…

In the case of level crossing ID 2309, QR had no interface agreement with the road manager(s) and therefore it was responsible for the maintenance of the approach roads within the rail corridor (also see Level crossing interface agreements).

Maintenance of level crossing ID 2309

QR records showed that in October 2011, repair work was undertaken to eliminate longstanding drainage issues at level crossing ID 2309. In addition, the approach roads to the level crossing were upgraded (Figure 4).

Figure 4: Dunkeld Access Road / level crossing ID 2309 upgrade in October 2011

Figure 4: Dunkeld Access Road / level crossing ID 2309 upgrade in October 2011. The images show the condition of the approach road surface on the day of the upgrade (October 2011). 
Source: QR

The images show the condition of the approach road surface on the day of the upgrade (October 2011). Source: QR

In July 2012, an assessment of the level crossing identified problems with the condition of the crossing surface. In the July 2012 assessment report, there was an ‘Observations’ section and a ‘Proposals’ section. A comment in the ‘Observations’ section stated:

Crossing gravel surface is breaking up. Track is “pumping”[5] and contributing to surface deterioration… [Figure 5]

Figure 5: An image taken by the assessor during the July 2012 assessment of level crossing ID 2309

Figure 5: An image taken by the assessor during the July 2012 assessment of level crossing ID 2309. The assessors report recorded that the crossing gravel surface is breaking up and the track is ‘pumping’ and contributing to surface deterioration. 
Source: QR

The assessors report recorded that the crossing gravel surface is breaking up and the track is ‘pumping’ and contributing to surface deterioration. Source: QR

In the ‘Proposals’ section of the report, the assessor noted:

Repair gravel surface in accordance with QR Standard Drawing No.2586. Carry out track maintenance works to address track ‘pumping’ issue.

Queensland Rail’s Standard Drawing No.2586, as referred to by the assessor in the report, is a civil engineering standard for public level crossings. In part, it stated:

Road pavement to be sealed with asphaltic cement or a similar material for a minimum distance of 10m on both sides of the railway.

An asphaltic cement prevents road surface deterioration, which is common with gravel-based road surfaces, particularly when the approach road is steeply inclined as it was at level crossing ID 2309. In addition, a sealed surface reduces the risk of low clearance vehicles striking the tracks as they cross. In the case of level crossing ID 2309, the assessor’s proposal was not actioned and the road surface remained unsealed (see Level crossing assessments).

Between October 2011 and the derailment in July 2017, there were two track defects recorded near the crossing:

  • a low priority defect recorded in November 2015, which went untreated until after the derailment
  • a critical track alignment issue recorded on 28 August 2016, which was rectified the following day.

Although the critical track alignment was not directly connected to the deteriorated condition of the level crossing, it is possible that the maintenance rectification work included some type of repair to the crossing surface. However, the extent of the repair work at the level crossing between July 2012 and August 2016 could not be determined based on the available records.

Accident site examination

Examination of approach roads

On 22 July 2017, the day after the derailment, the ATSB examined the accident site, which included the level crossing and approach roads to the crossing.

The approach roads to the level crossing were unsealed and constructed from compressed gravel road base. The on-site examination identified noticeable wheel furrows cut into the road surface on the approach to the level crossing from both sides (Figure 6).

Figure 6: The condition of the gravel-based road surface at the crossing on 22 July 2017

Figure 6: The condition of the gravel-based road surface at the crossing on 22 July 2017. The images show the deteriorated state of the road surface and evidence of wheel furrow marks cut into the road surface. 
Source ATSB

The images show the deteriorated state of the road surface and evidence of wheel furrow marks cut into the road surface. Source ATSB

Australian Standard 7658:2012 Railway Infrastructure: Railway Level Crossings stated:

The level crossing surface shall be flush with the top of rail, planar[6] between the two rails and flush with the approach roads.

When inspected by the ATSB following the derailment, the head of each running rail at the level crossing was standing noticeably proud above the crossing surface. In some areas, the web[7] of the rail was exposed (although see Examination of rail track). This was particularly noticeable where the wheel furrows in the road surface intersected with the rail lines (Figure 7).

Figure 7: The exposed railhead and rail web at level crossing ID 2309

Figure 7: The exposed railhead and rail web at level crossing ID 2309. The images show the deteriorated condition of the crossing surface with the railhead and some of the rail web exposed. The image on the left is the approach from the Warrego Highway and the image on the right is the approach from McKenzie Road. 
Source: ATSB

There was evidence on both sides of the approach road of a pair of dual wheel tread marks, consistent with a large road vehicle having recently passed over the crossing. The tread marks followed the path of the wheel furrows. There was no evidence of gouge/score marks in the gravel-based road surface between the wheel furrows approaching the rail lines on either side of the crossing surface.

To provide guidance for underbody clearance for rolling stock and road vehicles at level crossings, QR developed civil engineering drawings. Level crossing civil drawing No.2587 defined road-grading limits at private level crossings. Where the approaches to a level crossing had a maximum incline of 6 per cent, the crossing surface design was to exhibit a level plane for 3,000 mm on either side of the track centre line.[8]

The rail track in the area near the level crossing was elevated above the surrounding terrain. Measurements using a laser scanner identified that the approach roads (Dunkeld Access Road) on either side of the level crossing were inclined at about 5 per cent. However, the crossing surface did not exhibit a level plane on either side of the track centre line in accordance with the civil engineering drawing No. 2587. That is, the 5 per cent incline in the approach roads extended all the way up to the edge of the sleepers.

Examination of rail track

The site examination identified lateral displacement to the rails and significant gauge variation at the level crossing. There were side impact marks to the head of each rail at the point of lateral displacement.

The rail on the Warrego Highway side of the level crossing, which took the initial impact, was broken at the impact mark. The matching impact mark to the head of the parallel rail showed distortion to the gauge face, resulting in a gauge disparity of 55 mm (Figure 8).

Figure 8: Damage to the rails at level crossing ID 2309

Figure 8: Damage to the rails at level crossing ID 2309. The image shows corresponding impact marks in the head of each rail, which distorted the gauge and compromised the track integrity. Source: ATSB

The image shows corresponding impact marks in the head of each rail, which distorted the gauge and compromised the track integrity. Source: ATSB

The impact marks to each rail were located in the middle of the level crossing, between the wheel furrows made by road vehicles as they passed over the level crossing.

The impact marks covered the entire height of the head of each rail. Together with the absence of gouging/scoring in the road surface, this confirmed that the head of the rails were exposed at the point of impact.

As noted in Examination of approach roads, the site examination identified that the web of each rail was partially exposed at the level crossing and was clearly visible above the crossing surface. This was at least partly due to the low clearance vehicle colliding with the rails together with the derailment lifting the rails and displacing the gravel-based material previously surrounding the rails. Therefore, the extent to which the rail webs had been exposed, prior to the impact, was not able to be determined. However, it was noted that, where the wheel furrows intersected with the rails, the top of the rail webs had a distinctly different appearance to the lower sections of the webs, indicating that they had been exposed for some time.

Laboratory testing of a section of the damaged rail and the analysis of fracture propagation marks indicated that a factor external to the rail environment was involved in the lateral displacement of the rails. More specifically, the impact marks on each railhead indicated that the underframe of a low-clearance heavy road vehicle struck the track at some stage prior to the derailment. The impact marks confirmed that the road vehicle involved entered the level crossing from the Warrego Highway side.

Evidence relating to train activity on the day of the derailment confirmed that the condition of the track at the level crossing was free from damage at 1530. An empty coal train (9L16) passed through the level crossing at this time and did not encounter an issue with the track. Therefore, it is very likely that the underframe of a low-clearance heavy road vehicle collided with the rail infrastructure as it traversed the level crossing sometime between 1530 and 1557 on 21 July 2017.

Road vehicle information

Heavy road vehicle information

On the afternoon of 21 July 2018, the driver of a heavy road vehicle (prime mover and low-loader) was delivering a front-end loader to a worksite adjacent to the Devon Park Road level crossing just west of Oakey. QR had engaged a transport company to deliver the front-end loader to the worksite for the purpose of planned track maintenance work.

The heavy road vehicle was operating under the provisions of Guideline for Excess Dimension Vehicles Carrying Indivisible Articles in Queensland – Form Number 4 (Version 8) February 2013. The gross load capacity of the low-loader (trailer) was 55,000 kg, and the weight of the end-loader was under 20,000 kg. Therefore, the low clearance heavy road vehicle was not overloaded when traversing the level crossing.

The driver of the vehicle stated that he had delivered heavy earthmoving machinery to this location on many occasions. He further stated that on all occasions the same prime mover and low-loader combination had been used to deliver the machinery.

The driver stated he normally turned off the Warrego Highway at Devon Park Road to reach the worksite, passing over the level crossing and unloading the machinery on the northern side of the rail corridor. He added that he would then continue along McKenzie Road, and turn left at level crossing ID 2309 to gain access to the Warrego Highway (Figure 9).

Figure 9: The preferred route after delivering heavy machinery to the worksite

Figure 9: The preferred route after delivering heavy machinery to the worksite. The image shows the route normally taken by the driver of the heavy road vehicle after delivering earthmoving machinery for planned maintenance work during 2017. 
Source: Google Earth, annotated by the ATSB

The image shows the route normally taken by the driver of the heavy road vehicle after delivering earthmoving machinery for planned maintenance work during 2017. Source: Google Earth, annotated by the ATSB

However, on this particular occasion, due to traffic build-up at the Devon Park Road level crossing, the driver of the heavy road vehicle chose to use an alternate route. He chose to continue along the Warrego Highway, turn off at the next level crossing (ID 2309) and proceed along McKenzie Road in order to reach his destination.

In this instance, by travelling the alternate route, the low-clearance heavy road vehicle was passing over level crossing ID 2309 in a loaded condition, rather than an unloaded condition as it normally would. It was also entering the level crossing from a different direction to normal (that is, it was entering from the Warrego Highway side).

The driver of the heavy road vehicle stated that he recalled passing over level crossing ID 2309, but insisted that the vehicle did not collide with the rail infrastructure at the crossing.

Additional evidence relating to the movement of the heavy road vehicle

At about 1534 on 21 July 2017, video footage recorded by a camera fitted to a private vehicle travelling east on the Warrego Highway showed a prime mover and low-loader combination travelling west on approach to level crossing ID 2309. The heavy road vehicle was transporting a yellow front-end loader (Figure 10).

Figure 10: Dash camera footage from a private vehicle

Figure 10: Dash camera footage from a private vehicle. The image shows a prime mover and low-loader carrying a front-end loader as it approached level crossing ID 2309. The time stamped on the image is 1534:22 on Friday 21 July 2017. Source: private vehicle operator

The image shows a prime mover and low-loader carrying a front-end loader as it approached level crossing ID 2309. The time stamped on the image is 1534:22 on Friday 21 July 2017. Source: private vehicle operator

A short time later, a member of the public, who provided information to the local police, stated that he observed a prime mover and low-loader combination, transporting a front-end loader, come to a sudden stop as it passed over level crossing ID 2309 from the Warrego Highway side.

The witness stated that the heavy road vehicle appeared to have ‘bottomed-out’ on the crossing. He also stated that the driver of the heavy road vehicle left the driving cab of the prime mover and checked the underframe of the low-loader while it was stopped on the level crossing.

Reporting damage or safety incidents at level crossings

There were ‘incident reporting signs’ in place at the level crossing on the day the railway infrastructure was damaged. The signs provided an emergency contact number for reporting faults or safety incidents at the level crossing (Figure 11).

The Queensland Department of Transport and Main Roads has provided guidelines for the operation of excess dimension vehicles in Queensland. It detailed the responsibilities of the driver if a vehicle causes damage at a level crossing. It stated:

The driver of the vehicle must immediately report any damage caused to the asset owner and in the event that it presents a dangerous situation, to the local police.

On the day of the derailment, no advice of rail infrastructure damage at the level crossing was received by QR or the local police.

Figure 11: Incident reporting sign at level crossing ID 2309

Figure 11: Incident reporting sign at level crossing ID 2309. The image shows the incident reporting sign and the emergency contact number, in place at level crossing ID 2309 on the day of the derailment. 
Source: ATSB

The image shows the incident reporting sign and the emergency contact number, in place at level crossing ID 2309 on the day of the derailment. Source: ATSB

Inspections and assessments of level crossing ID 2309

Scheduled inspections of rail corridor

Inspection is the process by which QR collects and records information on the condition of the track and its components. Inspection must commence when the track is new and continue through its operational life.

QR’s Civil Engineering Track Standard, Module 1 – Track Monitoring, prescribed the regime to inspect the condition of the track[9] and track components in accordance with its standard. It lists three inspection types relevant to the inspection of track, each of which includes level crossings as an element for inspection. The three inspection types were:

  • Scheduled patrol inspection (maximum interval between inspections is 96 hours). On the Western Line, these inspections were conducted by a single infrastructure worker driving an on-track vehicle through the rail corridor. The inspection was to detail all elements within the rail corridor including level crossings, stopping as required to inspect recorded defects. A scheduled patrol inspection occurred on 20 July 2017, 1 day prior to the derailment, with no defects identified at level crossing ID 2309.
  • Scheduled general inspection (maximum interval between inspections is 4 months). On the Western Line, these inspections were typically conducted with two infrastructure workers, who travelled through the rail corridor using an on-track vehicle. The inspections detailed all elements within the rail corridor including level crossings, stopping as required to inspect recorded defects. The two scheduled general inspections undertaken prior to the derailment occurred on 16 January 2017 and 17 July 2017. Neither of the inspections identified issues at level crossing ID 2309.
  • Scheduled detailed inspection (maximum intervals between inspections was 48 months). These inspections were typically conducted by walking the rail corridor. In addition to the requirements for general inspections, detailed inspections must be at a level of detail sufficient to record the condition of the track for specific purposes such as determining required repairs or remedial actions. The last scheduled detailed inspection occurred on 18 May 2016, with no defects at level crossing ID 2309.

In accordance with QR’s Civil Engineering Track Standard, the infrastructure workers conducting these inspections were required to keep a lookout for obvious unsafe conditions, changed conditions or evidence of high rates of deterioration, which indicated unacceptable risk to operations.

Workers who conducted these inspections informed the ATSB that they stopped at all level crossings to inspect the lights, boom gates and guardrails where applicable. They advised that they also inspected the road surface and crossing surface of level crossings to ensure the safe passage of trains and vehicles. Workers advised that they could not readily distinguish between public and private level crossings without referring to documentation. Additionally, the infrastructure workers were unable to determine the balance of responsibilities of the rail infrastructure manager and the road manager at a level crossing if an interface agreement existed.

Level crossing assessments

QR undertook ‘assessments’ of level crossings

…to determine the appropriate level of control to reduce the risk of collision between a road vehicle/pedestrian and a train as far as is reasonably practicable.

QR’s Level Crossing Safety Standard MD-10-115 stated:

If a private crossing has substantial public use, the recognised level crossing risk assessment model (ALCAM) shall be used. For this purpose, public traffic is defined as vehicular traffic which is not owned or strictly controlled by the Responsible Road Manager…

Private, maintenance and temporary construction level crossings will be reviewed by Queensland Rail at not more than five yearly intervals. These reviews shall be carried out to ensure compliance with the controls approved following the initial assessment for the crossing, and verify that the conditions applying at the time of the initial assessment are still current and the controls are still effective.

These level crossing assessments are separate from the scheduled inspections of the rail corridor discussed in the previous section.

Documentation provided by QR showed that the last assessment/review undertaken at level crossing ID 2309 was on 2 July 2012. The next review should have occurred prior to 2 July 2017. However, this did not occur and, at the time of the derailment on 21 July 2017, the review was overdue.

A notation recorded by the assessor within the July 2012 assessment report stated:

Whilst at present this is a private (occupation) level crossing, it has been assessed as a public level crossing.[10]

The report was brief in nature, and there was no explanation within the report on the decision, for the purpose of the assessment, to upgrade the level crossing from private (occupation) to public. In accordance with the requirements for public level crossings in QR’s Level Crossing Safety Standard MD-10-115, the assessor used the Australian Level Crossing Assessment Model[11] (ALCAM) to evaluate the level crossing.[12]

QR’s level crossing database contains information relating to individual level crossings. After an assessment/review or audit, the assessor updates the system by populating information into the values and fields sections relevant to the level crossing. The system has the capacity to produce a characteristics report. The report reflects on the condition and characteristics of the level crossing at the time of the last entry.

On 15 August 2017, at the request of the ATSB, QR provided the latest characteristics report relating to the level crossing. The last recorded entry date in the comments section of the level crossing database was on 2 July 2012 (following the assessment). In part, the characteristics report stated the crossing condition was ‘bad’.

Based on the evidence supplied by QR, there was no record entered into QR’s asset management database to indicate whether any action regarding the assessor’s proposals in July 2012 to repair the approach road and crossing surface in accordance with QR Standard Drawing No.2586 (see Maintenance of level crossing ID 2309) was approved or actioned. Other proposals in the assessment report (such as installing advance warning signage and incident reporting signage) were actioned at some stage, but not recorded as being actioned in the asset management database.

Other level crossings

The ATSB did not conduct a detailed review of other level crossings in the area. However, it did examine level crossing ID 2310, located 1.5 km west of level crossing ID 2309. This was a private level crossing, and only supported traffic to and from a private property. There were noticeable wheel furrows on the approach roads. In addition, a significant portion of the railhead and web were exposed.

Level crossing interface agreements

An interface agreement is a written agreement between the rail infrastructure manager and road manager and sets out the responsibilities, mutual understanding and arrangement for the management of risks to safety at the shared level crossing interface.

Legislation, introduced in 2010 and current at the time of the derailment, stated the rail infrastructure manager (in this case QR) must identify, so far as is reasonably practicable, risks to the safety of persons arising or potentially arising from railway operations for a private road.

If the rail infrastructure manager forms the opinion that it is necessary to manage the identified risk in conjunction with the responsible road manager, the rail infrastructure manager should reasonably seek to enter into an interface agreement with that responsible road manager.

Alternatively, if the rail infrastructure manager forms the opinion that it is not necessary to manage the identified risks in conjunction with the responsible road manager, then the rail infrastructure manager for the road should keep a written record of the reasons for forming that opinion. The legislation stated that a responsible road manager for a private road meant the owner of the road.[13]

The Dunkeld Access Road was a private (occupation) road passing over a railway. It joined two public roads, the Warrego Highway and the nearby McKenzie Road (Figure 2). In effect, QR was the road owner within the rail corridor and was responsible for the inspection and maintenance of the level crossing. In addition, there is evidence that QR was maintaining the Dunkeld Access Road outside the boundary of the rail corridor.

At the request of the ATSB, QR provided correspondence stating that there was no interface agreement with a responsible road manager for level crossing ID 2309. There was also no evidence provided to indicate that QR had attempted to enter into an interface agreement with either the owner of the nearby property or a road authority. Nor was there a written record regarding the reason QR chose not to manage the risks in conjunction with a responsible road manager.

__________

  1. A private (occupation) level crossing is used to provide access to private land either from one part of the property to another or to access the property from a dedicated road for use by the responsible road manager (property owner) and their invitees only.
  2. The land on which a railway is built; comprising all property between property fences, or, where there are no fences, 10 m from the outside rail of the outside track.
  3. Pumping refers to the vertical movement of the track under the movement of rail vehicles.
  4. A flat two-dimensional surface.
  5. The web of the rail is the vertical section that supports the railhead.
  6. A level crossing surface helps minimise the potential for the rail line to be damaged by low clearance vehicles passing over the rails. Civil engineering drawing No.2587 stated that the approach roads for private crossings could be made from compressed gravel. Civil engineering drawing No.2586, which applied to public level crossings, had the same requirements for incline and crossing surface, but it also required an asphalt or similar surface.
  7. ‘Track’ meaning all the features on the right of way, excluding: bridges, culverts, signals, electrical infrastructure and buildings.
  8. A public crossing is a level crossing provided to maintain continuity of a public vehicular thoroughfare across a railway at grade and available for use by the general public.
  9. ALCAM is an assessment tool used to identify key potential risks at level crossings and to assist in the prioritisation of crossings for upgrades. The risk model is used to support a decision making process for both the road and pedestrian level crossings and to help determine the most cost-efficient treatments.
  10. MD-10-115 stated that the assessment of private crossings was to be conducted using a ‘Private & Queensland Rail Maintenance Level Crossing Assessment Report Form’. However, it also stated ‘Private crossings that are substantially used by members of the public shall be assessed using ALCAM.’
  11. The legislation had similar requirements for public roads, but stated that the rail infrastructure manager must reasonably seek to enter into an interface agreement with the responsible road manager. The legislation stated that a responsible road manager for a public road could be the local government or state government.

Safety analysis

Introduction

The loaded coal train derailed at level crossing ID 2309 due to the misalignment of the rail track. No factors associated with the operation of the train or the rolling stock contributed to the derailment.

This analysis will discuss the factors associated with the rail track misalignment. These include the condition of the level crossing, the collision of a heavy road vehicle with the rail infrastructure, the absence of reporting the collision and the processes used to ensure the condition of the level crossing.

Condition of level crossing ID 2309

The railway track at the level crossing was elevated above the surrounding terrain. The approach roads on either side of the level crossing were inclined at about 5 per cent, which was within but close to the maximum allowed incline of 6 per cent. This incline, and the fact that the road and crossing surface were constructed of compacted gravel-based material, meant the crossing was vulnerable to erosion and deterioration.

The available evidence suggests that local traffic and heavy road vehicles used the crossing, and the condition of the level crossing deteriorated over a period of time. The assessment of the level crossing in July 2012, 8 months after a comprehensive upgrade in October 2011, noted that the crossing surface was breaking up and deteriorating. The report included a proposal to replace the gravel-based road surface with asphalt or a similar sealed surface, but this was not done. It is possible some repair of the gravel-based road surface was done at this time, or after this time, such as when a critical track irregularity was identified and repaired in August 2016. However, the extent of any repair work could not be determined based on the available records.

An examination of the level crossing on 22 July 2017, the day after the derailment, identified that the approach roads to the level crossing were in a deteriorated state. There were significant wheel furrows in the gravel-based approach roads, which lowered the underframe of vehicles relative to the road surface, if they followed the furrows. In addition, there was not a level plane over the crossing surface, with the 5 per cent incline in the approach roads extending up close to the rails. The available evidence also indicated that the head and probably some of the web of each rail was exposed above the crossing surface, although the extent the webs were exposed could not be determined. Collectively, these factors, in the period leading up to the derailment, presented a significant risk associated with low-clearance road vehicles and agricultural machinery passing over the level crossing and damaging the rail infrastructure.

Collision with rail infrastructure at level crossing ID 2309

An examination of the accident site identified identical impact marks to the head of each rail at the level crossing. The lateral impact distorted both rails resulting in misalignment of the rail track. Analysis of the marks indicated that they were the result of impact from a low-clearance road vehicle that turned off the Warrego Highway and passed over the level crossing from that direction. The available evidence also indicated that the collision occurred between 1530 and 1557 (just prior to the train reaching the crossing).

It is very likely that the vehicle involved in the collision was the low-clearance heavy road vehicle (prime mover and low-loader combination) delivering the front-end loader to a worksite on the northern side of the rail corridor. It was observed approaching the level crossing at 1534, and a witness saw the low-clearance road vehicle come to a sudden stop at the level crossing shortly after.

It is possible that another low-clearance heavy road vehicle was involved in the collision. However, no other vehicles were sighted passing over the level crossing in the relevant period. In addition, although the same low-clearance heavy road vehicle had crossed the level crossing on previous occasions without incident, it is notable that on those occasions it had crossed without a load and crossed from the other direction.

Collision with rail infrastructure not reported

The heavy impact marks to the head of each rail and the resulting rail infrastructure damage suggests that the collision was significant. Therefore, it is highly likely that the driver of the low-clearance heavy road vehicle that caused the damage would have been aware that the vehicle struck the rail track.

Any damage to rail infrastructure such as rail track misalignment can have very adverse consequences. Accordingly, it is vitally important that any suspected damage is reported as soon as possible. The requirements for reporting such damage have been promulgated, and were also posted at the level crossing. In this case, had the damage been promptly reported, it is likely that advice of the potential problem could have been provided to the train crew prior to the train reaching the level crossing.

Scheduled inspections relating to level crossing ID 2309

The fact that the level crossing had deteriorated outside safe operating parameters suggests it was not being appropriately maintained. It is possible that the condition of the level crossing had only recently deteriorated. However, the level of deterioration that occurred between the upgrade in October 2011 and the assessment in July 2012 suggests that the crossing had a significant potential to degrade over time. The available information suggests that road vehicles, including heavy road vehicles, regularly used the level crossing. Together with factors such as the relatively steep incline and the gravel-based surface, this created the potential for degradation of the crossing surface and the approach roads.

In order for the level crossing to be maintained, the deterioration had to be detected through an assessment or review or scheduled inspections. The last assessment was conducted just over 5 years before the derailment. If an assessment had been done on or just prior to the scheduled date, it is likely that it would have detected the deterioration. Nevertheless, a slight extension to the 5-year timeframe would not be unreasonable in most circumstances (if requested). In addition, there was the significant potential for the problem with the access roads to have developed within 5 years. Therefore, the scheduled inspection processes played an important role in detecting problems before they reached a significant level of deterioration.

According to QR’s documented procedures, level crossing ID 2309 should have undergone a series of scheduled inspections at 96-hour, 4-month and 48-month intervals. The level of detail required in each inspection varied, but they all required aspects of the level crossing, including the road surface within the rail corridor, to be examined.

Overall, there should have been more than 540 combined inspections undertaken at the level crossing between the upgrade in October 2011 and the derailment in July 2017. A number of different personnel would have undertaken these inspections. However, none of these inspections identified the deterioration of the level crossing, which strongly indicates that the inspection process for detecting deficiencies associated with the approach roads and level crossing surface was inadequate. The ATSB also notes that the condition of the approach roads of another private level crossing, located near ID 2309, also had deteriorated to the extent that a significant portion of the railhead and rail web was exposed.

The benefit of an interface agreement

Other than an indemnity agreement between a local property owner and the Commissioner for Railways in 1947, there is no record of an interface agreement involving QR and a road manager(s) at level crossing ID 2309. In the absence of an interface agreement with the road manager(s), QR’s responsibility within the rail corridor was to monitor, inspect and maintain the condition of the road and level crossing throughout their operational life.

Alternatively, QR could have entered into an agreement with another entity to manage the road at the level crossing. As the level crossing forms a connection between a local council road and national highway, the responsible road manager could be either the local road authority, state government or both.

Although level crossing ID 2309 was classified as a private (occupation) level crossing, its unrestricted access as a thoroughfare between two public roads likely presented a level of risk similar to that of a public road crossing. The available evidence also indicates it was frequently used as a public road. In addition, the person who undertook the assessment of the level crossing in July 2012 conducted the assessment as if it was a public crossing. This presented an opportunity for QR to reconsider its classification of the crossing, and/or consider entering into an interface agreement with a responsible road authority.

The benefit of an interface agreement is that both QR and the road manager(s) would have shared the identified risks through a controlled process. Accordingly, if responsibilities for inspecting the condition of the road surface by a road manager at regular intervals was appropriately documented and controlled, this could have increased the potential to identify the developing problem.

However, without knowing exactly how the responsibilities within the rail corridor would have been documented and controlled, it is difficult to determine whether an interface agreement by itself would have led to the identification of the deterioration in the approach road and crossing surface on Dunkeld Access Road prior to the collision with rail infrastructure and subsequent derailment. Ultimately, QR was still responsible for inspecting the approach roads within the rail corridor, and had not identified the deterioration.

It should be noted that the QR network has more than 1,000 private level crossings. A substantial number of these do not have an interface agreement. Consequently, QR’s inspection processes need to be adequate when inspecting approach roads and crossing surfaces at such locations.

Findings

From the evidence available, the following findings are made with respect to the derailment of train 9869 at level crossing ID 2309, near Oakey, Queensland on 21 July 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.

Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.

Contributing factors

  • The condition of level crossing ID 2309 was degraded, with significant wheel furrows in the approach roads, the absence of a level plane over the crossing surface, and the head of both rails was exposed. Some of the web of the rails was also probably exposed.
  • It is very likely that the underframe of a low-clearance heavy road vehicle collided with the exposed head of the rails as the vehicle traversed level crossing ID 2309.
  • As a result of the collision by a low-clearance heavy road vehicle, the rail lines at level crossing ID 2309 were laterally displaced, creating the potential for a derailment.
  • The driver of the low-clearance heavy road vehicle that collided with and damaged the rail infrastructure at level crossing ID 2309 did not report the occurrence to the relevant authorities.
  • Queensland Rail’s track monitoring and inspection processes were not effective in identifying significant deterioration in the condition of level crossing ID 2309 and its approach roads to ensure the safe operating limits of the level crossing throughout its lifecycle. [Safety issue]

Other factors that increased risk

  • Queensland Rail had not entered into an interface agreement with a responsible road authority at level crossing ID 2309, even though Dunkeld Access Road and the level crossing were in effect being used as a public thoroughfare. It is likely that an interface agreement would have resulted in a co-ordinated approach to managing the shared risks at the level crossing.

Safety issues and actions

The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.

Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the rail industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.

All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.

Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.

QR’s track monitoring and inspection processes

Safety issue number: RO-2017-007-SI-01

Safety issue description: Queensland Rail’s track monitoring and inspection processes were not effective in identifying significant deterioration in the condition of level crossing ID 2309 and its approach roads to ensure the safe operating limits of the level crossing throughout its lifecycle.

Additional safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Queensland Rail

Following the derailment, Queensland Rail (QR) repaired the level crossing. During this repair, a sealed asphalt road was installed, covering both sides of the crossing surface.

In its response to the draft investigation report in April 2019, QR advised that since the derailment it had attempted to enter into an interface agreement with a local land owner (who did not want the crossing closed) and the local council (who did not want to make the crossing public).

In April 2019, QR also advised the following in relation to interface agreements:

QR has an audit programme in place to assess all private crossings, upgrade them to the QR standard as necessary, and seek to enter into interface agreements.

QR have requested that the land owner for this crossing enter into an interface agreement with Queensland Rail for the safe operation and use of this level crossing.

An Interface Agreement for Occupational Crossing ID 2309 (Dunkeld Access Road, Oakey (38.62km Western Line) was sent to the private land owner on 9 April 2019. Receipt of the letter was acknowledged on 15 April 2019.

In relation to the ongoing audit programme, audits so far have been completed within the North, Central, North Coast/ Wide Bay/ Burnett regions of Queensland. To date, the audits have identified 72 crossings for closure (as they are no longer required by any party), 28 crossings will be changed from private to public status crossings (as they appear to be used by the general public), 7 crossings will be changed from private to maintenance status crossings and 3 crossings have been identified as requiring relocation. Also to date, licence/interface agreements for 411 have been sent to relevant parties in the regions noted above and 174 licence/interface agreements have been formalised.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • Aurizon (train operator)
  • Queensland Police Service
  • Queensland Department of Transport and Main Roads
  • Queensland Rail (track owner)
  • rail traffic crew of train 9869.

Submissions

Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to Queensland Rail, the driver of the heavy road vehicle, the operator of train 9869 (Aurizon), the crew of train 9869 and the Office of National Rail Safety Regulator (ONRSR).

A submission was received from Queensland Rail. The submission was reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2019

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number RO-2017-007
Occurrence date 21/07/2017
Location 8 km west of Oakey
State Queensland
Report release date 26/06/2019
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Rail
Rail occurrence category Derailment
Occurrence class Accident
Highest injury level None

Train details

Train operator Aurizon
Train number 9869
Type of operation Bulk coal
Departure point Acland coal siding near Jondaryan, Queensland
Destination Port of Brisbane, Queensland
Train damage Substantial

Signal irregularity at Islington Junction, New South Wales, on 25 May 2017

Discontinuation notice

Report release date: 08/05/2019

Section 21 (2) of the Transport Safety Investigation Act 2003 (TSI Act) empowers the Australian Transport Safety Bureau (ATSB) to discontinue an investigation into a transport safety matter at any time. Section 21 (3) of the TSI Act requires the ATSB to publish a statement setting out the reasons for discontinuing an investigation.

On 25 June 2017, the ATSB commenced an investigation into a near collision between a Track Maintenance Vehicle (TMV) NK83 and freight train 4190N due to a signal irregularity at Islington Junction, NSW.

At approximately 1020 (AEST) on 25 May 2017, a TMV NK83 travelling to Port Waratah was stopped by the Australian Rail Track Corporation (ARTC) train control at Signal IJ25. The crew in the rear locomotive of NK83 noticed that although they were foul of the Up main, the signals were clear for rail traffic to pass through. Soon after this, freight train 4190N was seen operating on the Up main headed towards NK83. The crew in the rear locomotive of NK83 made an urgent request to move NK83 forward to avoid a being struck by 4190N. NK83 moved forward and avoided being struck by 4190N.

ATSB’s preliminary evidence collection revealed:

  • The signalling system at Islington junction was upgraded in 2007. The upgrade of the interlocking system did not include a risk control which previously prevented conflicting train movements at the junction.
  • ARTC have since changed the interlocking system to manage the risk of conflicting movements at Islington Junction.
  • Since the incident, ARTC have inspected similar crossings and confirmed that the missed interlocking risk control was isolated to the crossing at Islington Junction.

Following ARTC’s confirmation that the incident was isolated to the crossing at Islington Junction, the ATSB considered it was unlikely that further ATSB investigation would identify any systemic safety issues. As such, the ATSB has discontinued this investigation.

Occurrence summary

Investigation number RO-2017-002
Occurrence date 25/05/2017
Location Islington Junction
State New South Wales
Report release date 08/05/2019
Report status Discontinued
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Rail
Rail occurrence category Signal Irregularity
Occurrence class Incident
Highest injury level None

Train details

Train operator Pacific National
Train number NK83
Type of operation Track Geometry car AK car
Departure point Broadmeadow, New South Wales
Destination Kooragang, New South Wales
Train damage Nil

Train details

Train operator Pacific National
Train number 4190N
Type of operation Intermodal
Departure point Brisbane, Queensland
Destination Sydney, New South Wales
Train damage Nil