On 18 August 2017, the pilot of a Robinson R44 II helicopter, registered VH-LGN, was conducting a private flight from Noonamah, Northern Territory (NT) to Channel Point, NT, with three passengers on board. At about 1400 Central Standard Time,[1] after a 20-minute flight, the helicopter was flying about 500 ft above a beach at Channel Point in preparation for landing. Weight and balance information provided by the pilot indicated that the helicopter’s centre of gravity was toward the forward limit but within the allowable range.
The pilot reported that the helicopter’s airspeed was about 50 kt as he commenced a descending right turn, intending to land on the beach. During this time, a ‘bounce’ developed through the airframe. The pilot initially moved the cyclic[2] aft to reduce airspeed, the bounce increased to a violent shaking, both fore and aft, and side to side. The pilot then moved the cyclic forward to increase airspeed and lowered the collective,[3] with the intent to conduct an immediate landing.
Just prior to landing, the pilot raised the collective and flared the helicopter. Despite this, the helicopter landed heavily, damaging the skids and the main rotor blade severed the tail boom. The helicopter stopped in an upright position and all four occupants vacated the helicopter without injury.
Related occurrences
The nature of the airframe shaking, as described by the pilot, was similar to an occurrence investigated by the United States National Transportation Safety Board (NTSB) (ANC09GA040) in 2009. In that occurrence, the pilot described severe vibrations and oscillations to the point where the pilot felt like the helicopter was going to come apart. The pilot conducted an emergency landing and landed hard, with the main rotor contacting the tail boom. The NTSB report noted several other similar occurrences of severe airframe vibration from 2006 and 2007, which also resulted in the pilots conducting emergency landings. The vibrations or oscillations have also been referred to as ‘mast rocking’ or ‘chugging’.
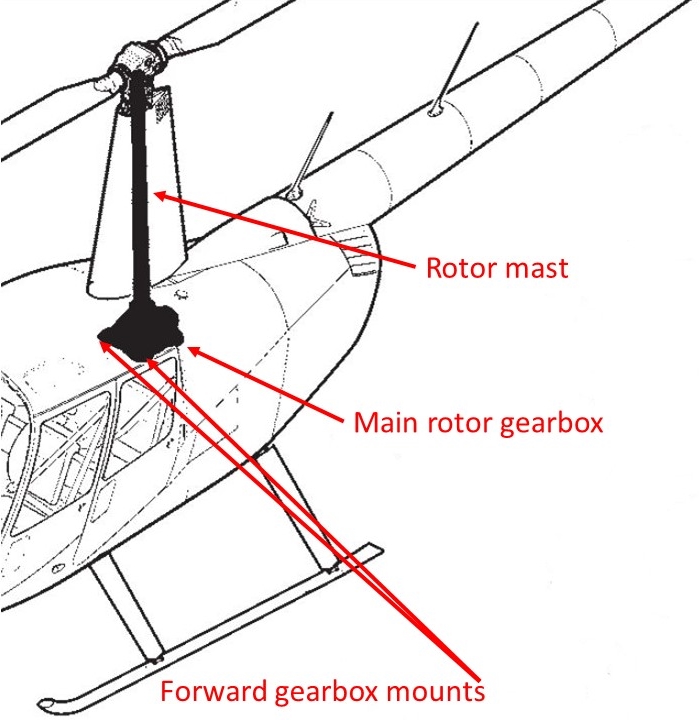
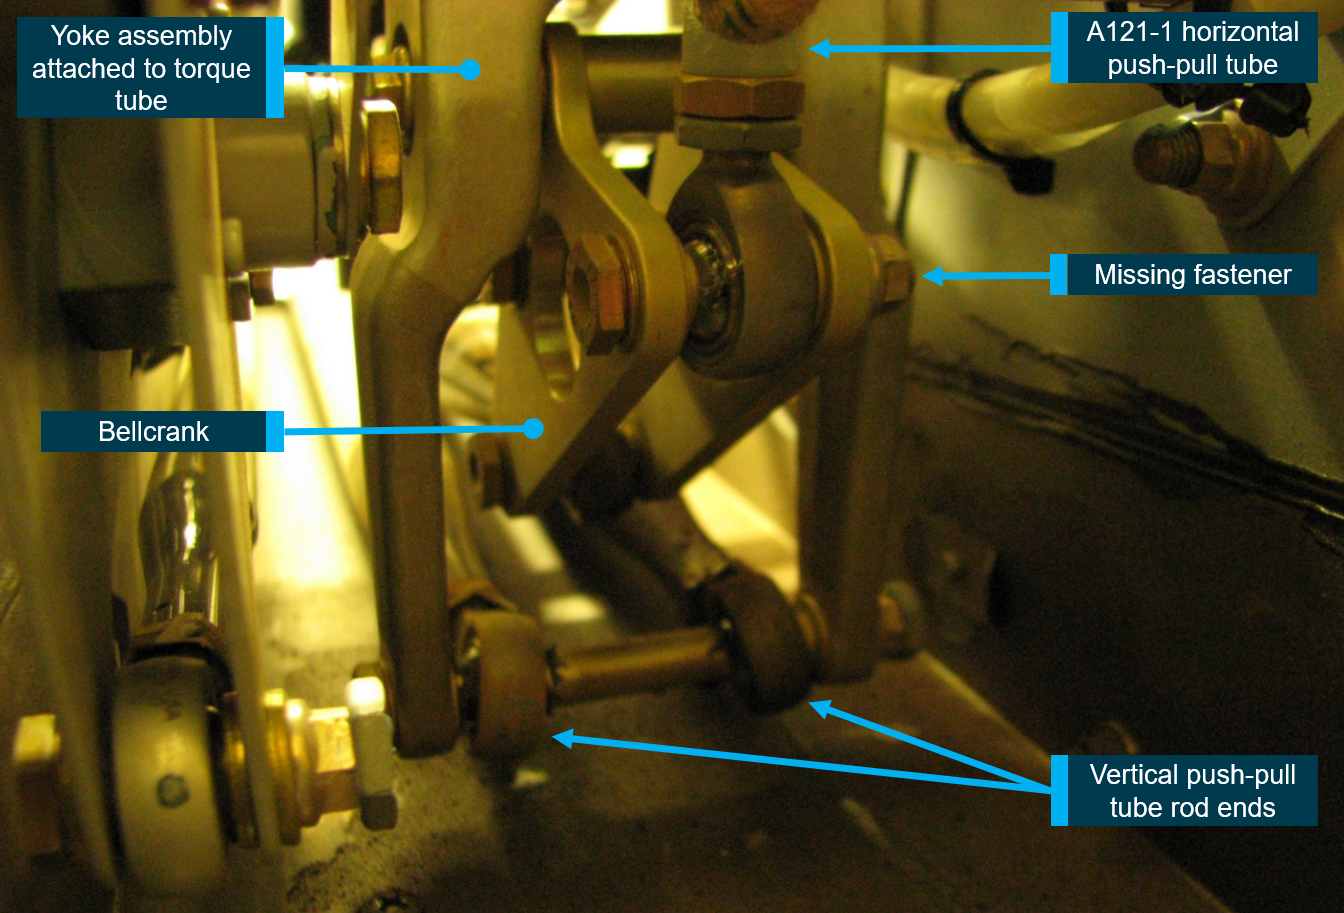
Based on information provided by Robinson Helicopters, the NTSB report indicated that the oscillation was associated with fore and aft movement of the rotor mast (Figure 1). The manufacturer had conducted flight tests related to the oscillations and determined that they ‘may develop during operation at high gross weight, at about 90-100 kt airspeed’. Additionally, the tendency to develop oscillations was exacerbated by flying with a forward centre of gravity (although still within the approved envelope) and by entering a 30° left banked turn. A right banked turn could also exacerbate the oscillation, but it was more easily initiated in a left turn.
The mast oscillation was attributed to lack of firmness of newly-installed gearbox mounts and the manufacturer introduced stiffer mounts (part number A653-2) in June 2007 to counter the problem. The rubber in the mounts was found to harden with heat and compression during service and the issue was therefore more likely to affect low-hour helicopters. As such, there was only a requirement to change to the new, stiffer mounts during routine replacement of the original (A653‑1) parts.
In relation to oscillations, the following information was incorporated as Safety Tip 19 in the Robinson R44 Pilot’s Operating Handbook (October 2011):
Use caution when loading the helicopter near the forward CG limit and remember that CG shifts forward as fuel is burned. Near the forward CG limit, a fore-aft oscillation may develop during steep turns or autorotations. To stop this oscillation, return to straight and level powered flight. Oscillation may take several seconds to dissipate.
Figure 1: Location of the main rotor gearbox and forward gearbox mounts
Source: Robinson Helicopter Company, modified by the ATSB
Helicopter maintenance
Review of maintenance documentation showed that VH-LGN had 1,609 hours total time in service and 45 hours since the last 100-hour inspection on 14 July 2017. The airframe logbook indicated that replacement of the main rotor gearbox transmission mounts was conducted at that service. The airframe logbook recorded that the forward main rotor gearbox transmission mounts were replaced with the incorrect (superseded) part number A653-1, instead of the required A653-2 parts.
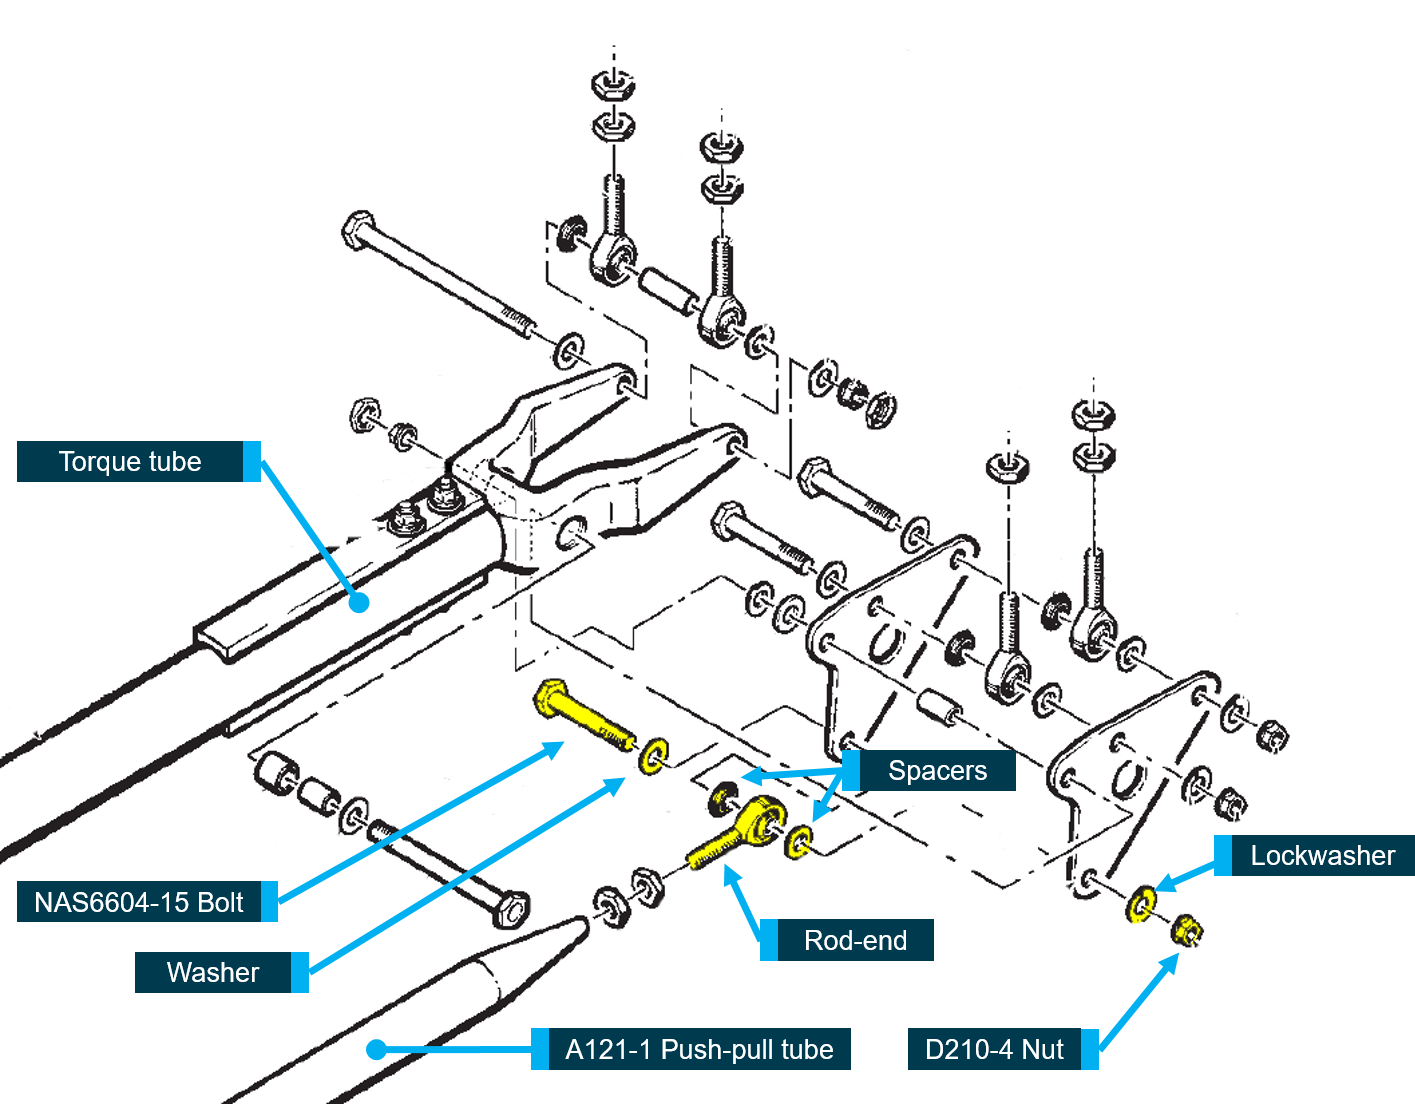
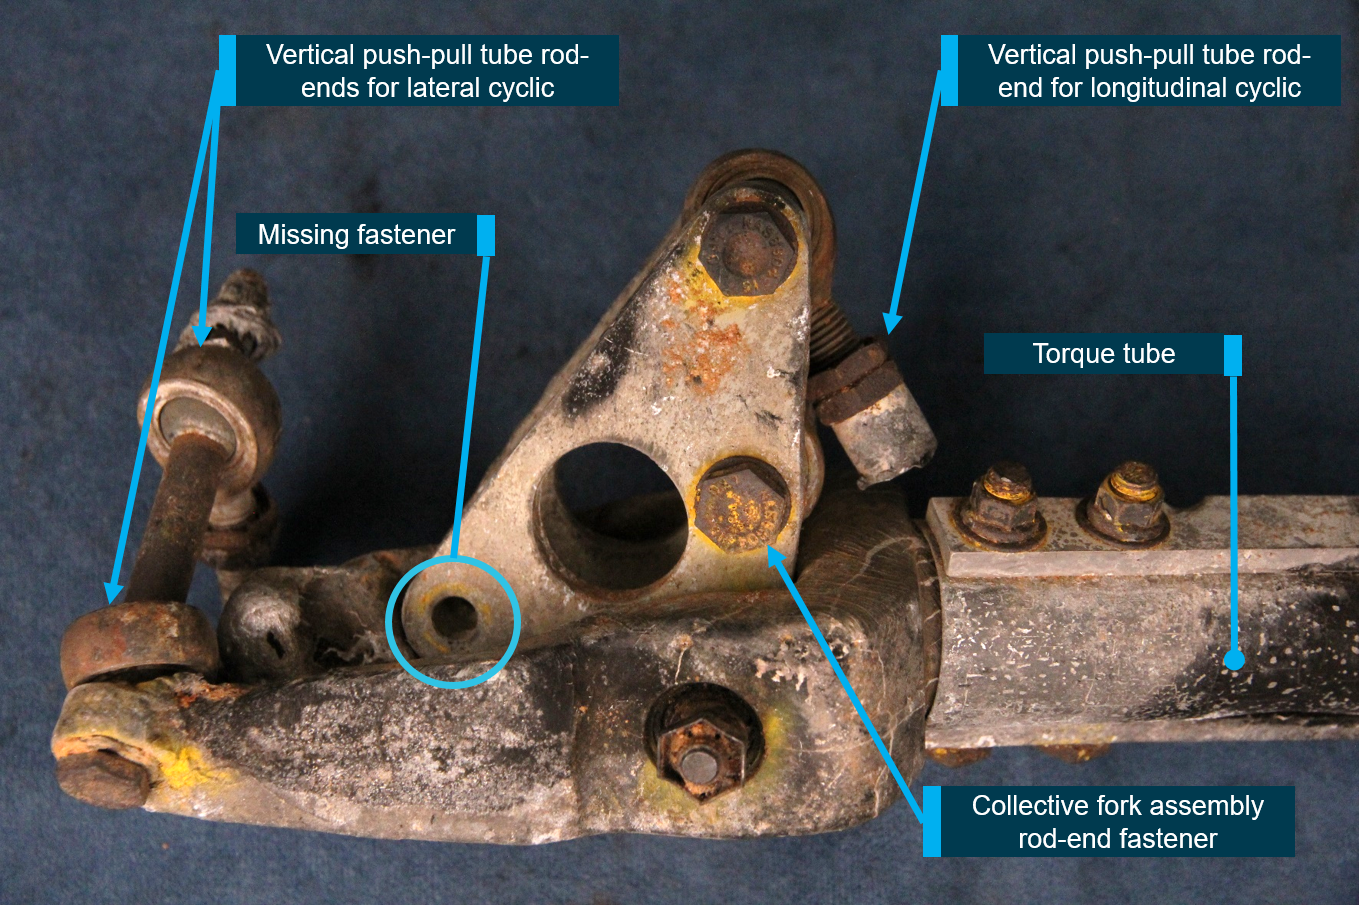
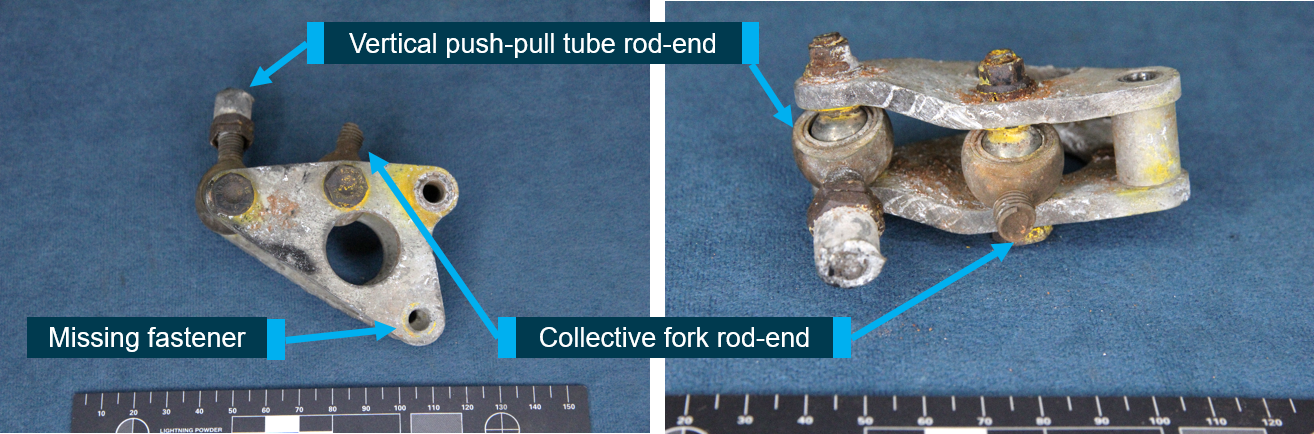
The A653-1 and A653-2 parts were the same size and shape. They were distinguished by the -2 parts having a large, handwritten ’H’ in yellow ink on the top and edge of the mount (Figure 2), in addition to the labelling on the parts’ packaging. The availability of the -1 part was due to their continued installation on the smaller, Robinson R22 helicopters. The engineer who had changed the mounts had referenced the correct maintenance information at the time, but was unable to recall or reconcile the circumstances that resulted in him obtaining and fitting the incorrect part number mounts.
Figure 2: A653-2 gearbox mount installed
Source: Robinson Helicopter Company
Analysis
The onset of the mast oscillations, as described during this occurrence, was largely consistent with the flight conditions described in Safety Tip 19 in the Robinson Pilot’s Operating Handbook. While the pilot’s actions in this occurrence did not follow the recommendation listed in the Safety Tip, his actions were consistent with those from previous occurrences and also in accordance with Safety Tip 7, which recommends making a safe landing if unusual sound or vibration begins in flight.
Incorrect forward main rotor gearbox mounts were installed in the R44 helicopter during recent maintenance. The manufacturer had previously found that these softer forward gearbox mounts increased the likelihood of the onset of oscillations associated with mast rocking in Robinson R44 helicopters. The onset of the airframe oscillations experienced by the pilot in this occurrence were therefore consistent with the manufacturer’s findings.
The circumstances that resulted in the installation of the incorrect parts was not clear. However, this type of error highlights the importance of extra vigilance around visually and dimensionally‑similar parts.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
As the pilot commenced a descending right turn, the unexpected onset of severe fore and aft mast oscillations resulted in the pilot conducting an immediate landing that significantly damaged the helicopter.
The maintainer had inadvertently installed incorrect forward main rotor gearbox mounts, which had previously been found to contribute to the initiation of fore and aft mast oscillation.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
At 1136, on 12 August 2017, The Airplane Factory Sling 4 amateur-built aircraft, registered VH-BEG, departed Caloundra Aerodrome, Queensland, for a local private flight. There was a pilot and three passengers on board.
At 1143, the flight returned to Caloundra. Pilots of other aircraft reported that at the time wind conditions were light and aligned with runway 05.
The pilot positioned the aircraft to join the circuit for runway 12. The pilot of another aircraft advised runway 05 was in use and the pilot of VH-BEG then manoeuvred the aircraft to join the circuit for runway 05. While on the final leg of the circuit, the pilot selected full flap and observed parachutists descending to the right of the runway 05 threshold.
As the aircraft approached the runway, the pilot became concerned that the parachutists might drift into the path of the aircraft and focussed on the location of the parachutists. He then detected that the aircraft had deviated above and to the right of the desired approach path. The pilot then reduced power to idle and commenced a forward slip[1] to attempt to increase the approach angle and regain the desired approach path. As the aircraft approached the runway 05 threshold, he stopped the forward slip and began a left turn toward the threshold.
During the left turn, the aircraft aerodynamically stalled and the aircraft rolled to the left. Almost immediately, the left wing tip struck the ground and the aircraft collided with terrain. The fuselage fractured at the engine firewall, the engine was pushed rearward and intruded into the cabin.
The aircraft came to rest inverted and was destroyed (Figure 1). The pilot and all three passengers suffered serious injuries.
The figure shows the wreckage of VH-BEG after emergency services had attended. Source: Queensland Police
Video footage
Video footage taken by the passenger in the left rear seat captured the final eight seconds of the flight.
The footage showed the aircraft in a forward slip with the nose yawed[2] to the right and tracking parallel to, but right of, the runway extended centreline (Figure 2). The indicated airspeed was 58 kt,[3] and the tachometer indicated idle power. The forward slip then stopped and the aircraft turned left toward the runway threshold. At the same time, the descent rate increased.
Figure 2: Images from video footage
The figure shows images of the aircraft during the approach prior to the accident. The aircraft is shown in a forward slip (left) and at the beginning of the turn toward the runway 05 threshold (right). Source: Passenger, annotated by ATSB
The aircraft approached the runway threshold on a heading of about 010 degrees magnetic, and appeared to be undershooting the threshold. Pitch angle then increased, an aerodynamic stall occurred, and the aircraft rolled rapidly left. As the aircraft rolled, the slip indicator displayed a full right deflection, indicating that the aircraft had entered an incipient left spin. The footage stopped as the left wing impacted the ground.
Pilot comments
The pilot of the aircraft provided the following comments:
The pilot reported calculating the weight and balance of the aircraft prior to the flight using the aircraft electronic flight instrumentation system (EFIS) and using average weights for all occupants. He recalled the EFIS showing the aircraft weight and balance to be within the approved range.
He did not consider conducting a go-around.
The aircraft was fitted with a stall warning system, however, this did not activate prior to the accident.
Aircraft weight and balance
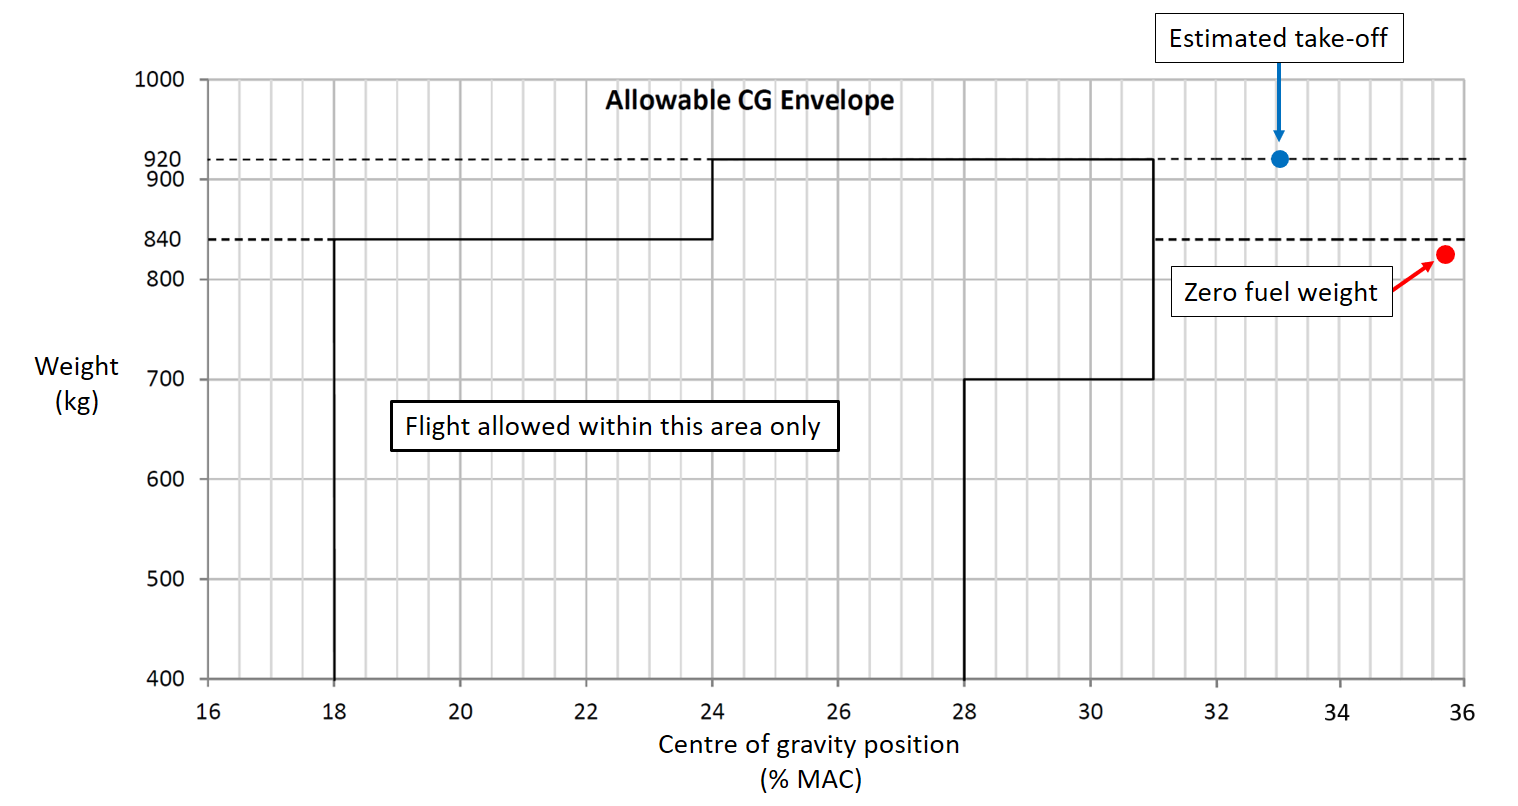
Weight and balance limitations were contained in the aircraft’s Pilot’s Operating Handbook (POH). The limitations defined the gross weight and centre of gravity limits. The maximum take-off weight of the aircraft was 920 kg and the aircraft was fitted with four seats.
The limits of the permissible centre of gravity range were defined as a percentage of mean aerodynamic cord (MAC):[4]
The forward limit of the permissible range was 18 per cent MAC up to a gross weight of 840 kg, above this weight, the forward limit was 24 per cent MAC.
The rear limit of the permissible range was 28 per cent MAC up to a gross weight of 700 kg, above this weight, the rear limit was 31 per cent MAC.
The empty weight of the aircraft was 461 kg. The weight of the front seat occupants was 190 kg and the weight of the rear seat occupants was 175 kg. The pilot estimated that at the time of take-off there was about 93 kg of fuel on board and reported that no items were carried in the baggage compartment.
Based on the above weights, the estimated take-off weight for the accident flight was 919 kg. The take-off centre of gravity position was 33.1 per cent MAC, and the zero fuel weight[5] centre of gravity position was 35.7 per cent MAC.
The centre of gravity position was outside of the permissible range for the entire flight (Figure 3).
Figure 3: Graphical representation of the aircraft centre of gravity for the accident flight
The graph shows the permissible centre of gravity range along with the calculated take-off and zero fuel weight centre of gravity positions. Source: Aircraft manufacturer, modified and annotated by ATSB
The pilot reported calculating the weight and balance to be within the permissible range using average weights.
The Civil Aviation Safety Authority advisory publication CAAP 235-1(1) Standard passenger and baggage weights provides the following guidance for using standard, or average, weights when calculating aircraft weight and balance:
Standard weights should not be used in aircraft with less than seven seats.
Because the probability of overloading a small aircraft is high if standard weights are used, the use of standard weights in aircraft with less than seven seats is inadvisable. Load calculations for these aircraft should be made using actual weights arrived at by weighing all occupants and baggage.
The New Zealand Civil Aviation Authority publication Weight and Balance contains the following information regarding the effects of operating an aircraft outside of the rear centre of gravity limit:
Your aircraft has centre of gravity limits, and any loading that puts the centre of gravity outside of those limits will seriously impair your ability to control the aircraft. The more aft the centre of gravity, the more unstable the aircraft. Forward pressure on the elevator control and full nose-down trim may be necessary to keep the aircraft from pitching up and stalling.
The further aft the centre of gravity is, the harder it is to recover from a stall.
ATSB comments
VH-BEG loading
Using the weight of the front seat occupants from the accident flight and allowing for no fuel and no baggage, the ATSB calculated that the maximum weight able to be carried in the rear seats of VH-BEG, while remaining within the allowable centre of gravity range, was just 118 kg. Using 105 kg of fuel as ballast, this weight increased to 148 kg. This allowed for 15 minutes of flight fuel and a 45-minute fuel reserve to be carried within the 920 kg maximum allowable take-off weight.
It was also found that when allowing for full fuel and any weight in the front two seats, the aircraft also required weight in the rear seats, or the baggage compartment, to ensure the centre of gravity was not located forward of the allowable range.
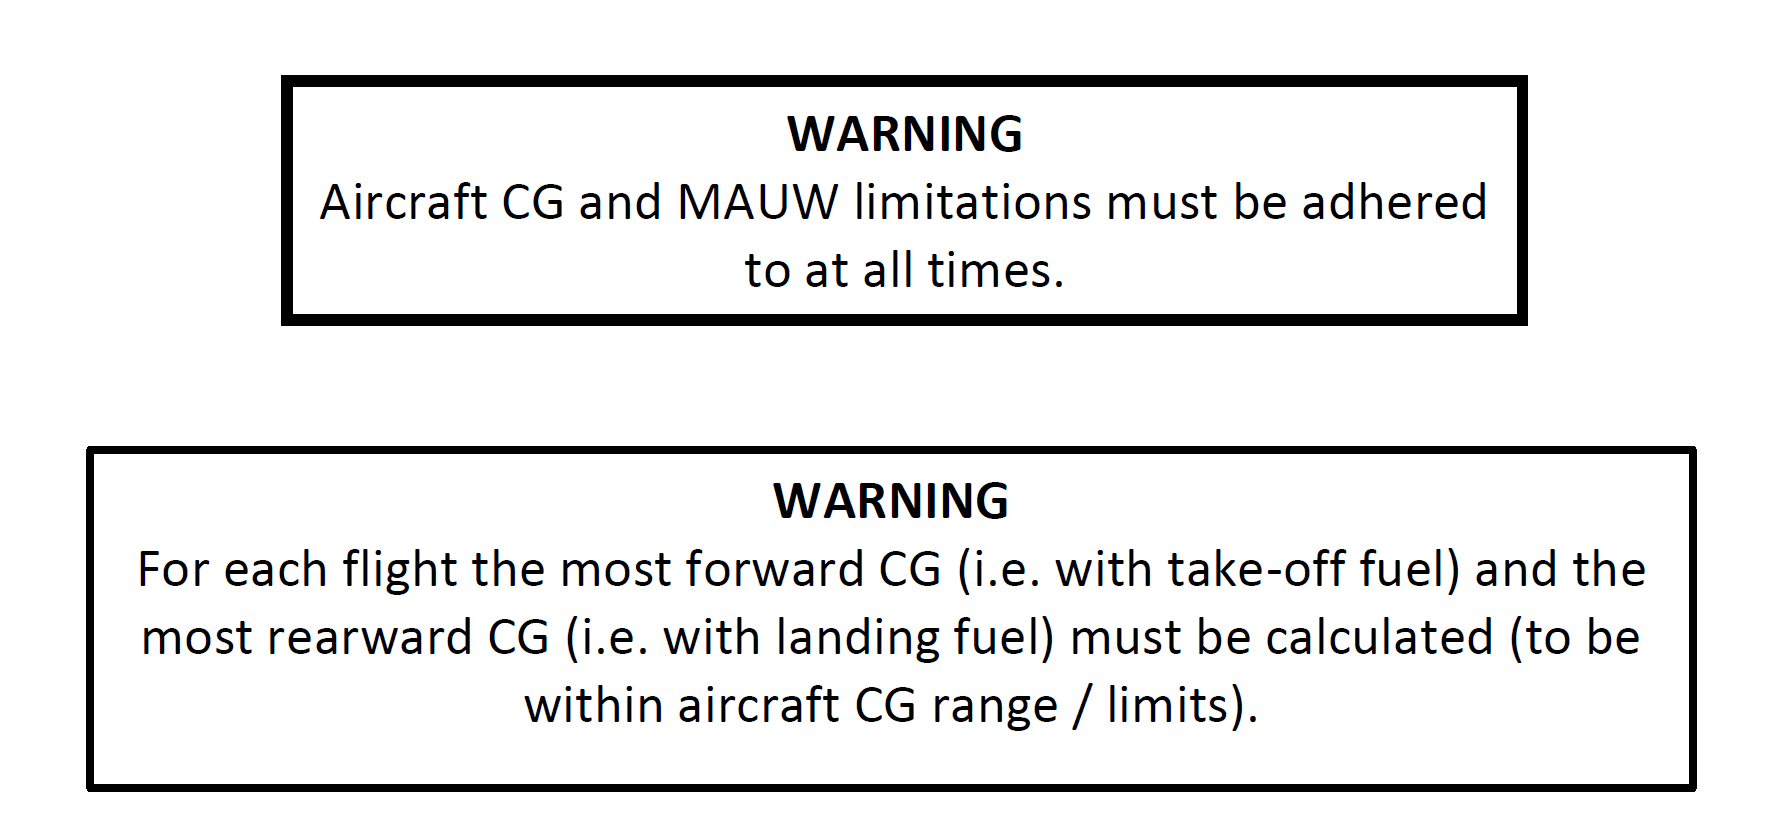
Warnings regarding weight and balance limitations included in the Sling 4 POH are shown in Figure 4:[6]
Figure 4: Warnings contained in POH
The figure shows warnings contained within the Sling 4 POH. Source: Aircraft manufacturer
Amateur-built aircraft regulations allow for some variance in construction which can lead to differences in the longitudinal balance and loading of individual aircraft. Pilots of amateur-built aircraft are reminded to be familiar with the weight and balance capabilities and limitations of their aircraft.
The weight and balance calculation blank form on page 6-13 lists the location of the front seats as 1959mm aft of the datum. The correct figure is 1902mm, as detailed on page 6-4.
The pilot did not use the POH to calculate the weight and balance, therefore the error did not contribute to the accident. However, pilots of Sling 4 aircraft should ensure that weight and balance calculations are conducted using the correct figure.
Safety analysis
The flight was conducted with the centre of gravity aft of the rear limit. This had the effect of making the aircraft less stable and more susceptible to an aerodynamic stall. This also made recovery from a stall more difficult.
After detecting that the aircraft had deviated from the desired flight path, the pilot attempted to continue the approach by manoeuvring the aircraft at low level and low speed. The aircraft was loaded outside of the permissible centre of gravity range, and the manoeuvring further reduced the remaining margins of controllable flight until the aircraft stalled and control was lost.
During the manoeuvring, the aircraft stalled and entered an incipient spin. The stall and incipient spin occurred at a height from which recovery was not possible and the aircraft collided with terrain.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The aircraft centre of gravity position was aft of the rear limit.
During the approach, the aircraft stalled and entered an incipient spin at a height from which recovery was not possible and the aircraft collided with terrain.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence:
Aircraft manufacturer
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety action:
Change to documentation
The position of the front seats in the blank form on page 6-13 of the Sling 4 Pilot’s Operating Handbook, version 1.6 will be corrected to show 1902mm aft of the datum.
Safety message
This incident highlights the critical importance of operating an aircraft within prescribed limitations at all times.
After detecting that the aircraft had deviated from the desired approach path, the pilot did not conduct a go-around. While the aircraft centre of gravity was located outside of the permissible range, a go-around, rather than manoeuvring at low speed and low level, may have prevented the accident from occurring.
The Flight Safety Foundation Approach-and-landing accident reduction tool kit Briefing note 6.1 – Being prepared to go around, stated that the importance of being go-around-prepared and go-around-minded must be emphasised because a go-around is not a frequent occurrence.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
At 2000 on 12 August 2017, the fishing vessel Mako departed San Remo, Victoria, bound for fishing grounds about 3 hours away. Once clear of Cape Woolamai, Mako maintained a steady course (210°) and speed to the south-west. At the same time, the container ship Glasgow Express was passing Cape Liptrap heading north-west. The ship was bound for Melbourne, Victoria, and was maintaining a steady course (299°) and speed. From about 2030 the vessels were on a collision course.
No avoiding action was taken by either vessel and, at about 2246, they collided.
What the ATSB found
The ATSB found that a proper lookout by ‘all available means’ was not being maintained on either vessel.
Glasgow Express’s bridge team saw and monitored Mako visually from about 2200. However, a full appraisal of the situation using other instruments or means available on the bridge (such as radar) was not done. As a consequence, the situation was misinterpreted and the risk of collision was not identified. Therefore, no avoiding action was taken.
Prior to handing over the watch at 2230, Mako’s watchkeeper identified Glasgow Express by radar and visually. However, the information was misinterpreted and it was concluded that the Glasgow Express was passing clear, ahead of the fishing boat, and no avoiding action was taken. Then, after taking the watch, Mako’s second watchkeeper did not see the Glasgow Express until moments before the collision.
In addition, Mako was under way with all external lights on. This made the vessel more easily seen, but reduced the ability for Glasgow Express’s bridge team to accurately visually appraise the situation. The bright lights also reduced Mako’s watchkeeper’s night vision and ability to distinguish features beyond the glare of the lights.
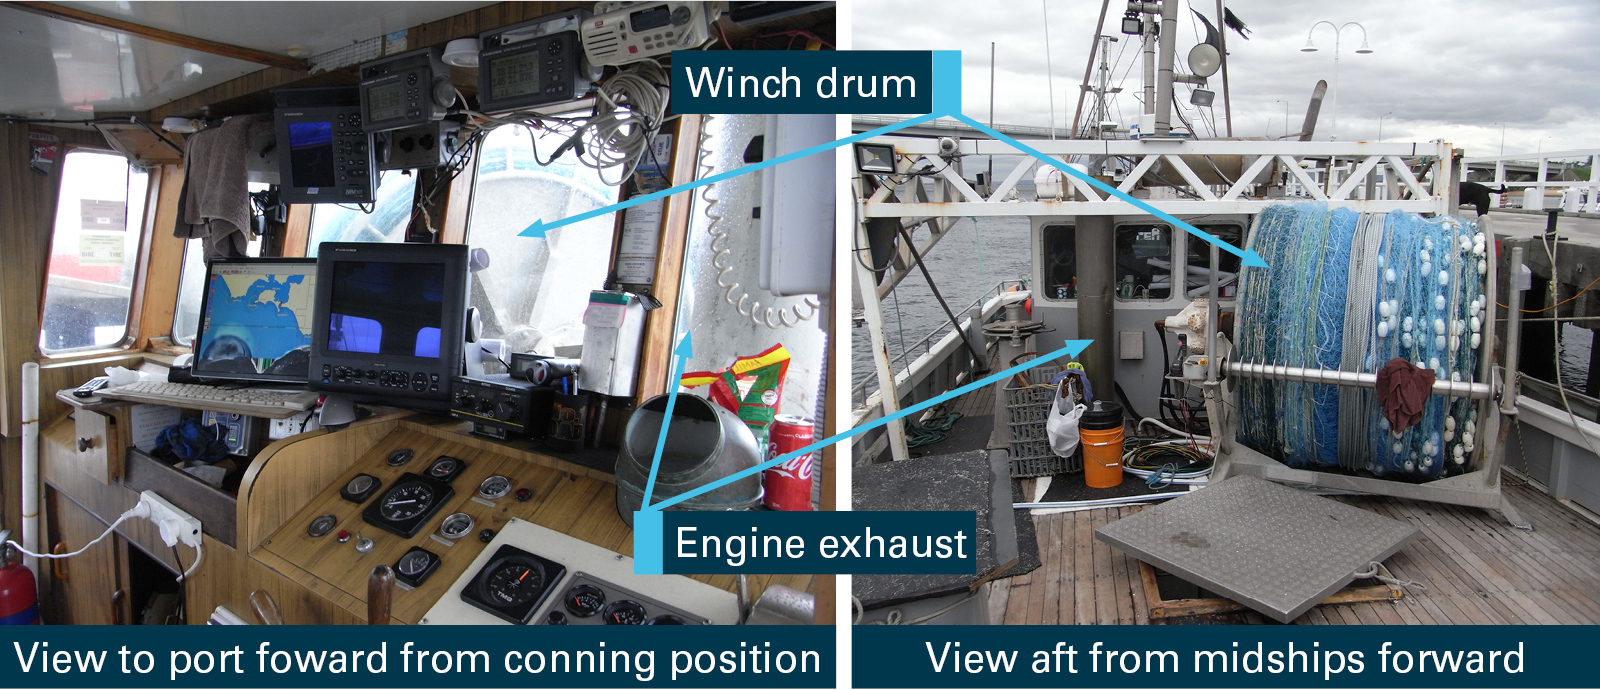
The ATSB also noted that Mako, similar to other fishing vessels of this design, had a large fishing net winch drum mounted on deck forward of the wheelhouse. This winch drum restricts forward vision and may limit the ability to maintain a proper lookout unless accounted for in on-board procedures and training.
What's been done as a result
Glasgow Express’s operator undertook a fleet-wide information and education program which outlined the incident and emphasised the need to use all available means to maintain safe navigation in accordance with the collision regulations.
Safety message
The ATSB continues to see collisions between trading ships and small vessels. A common contributing factor has been the failure to use all available means to accurately appraise a situation and the risk of collision.
The ATSB reinforces to masters, owners, operators and skippers of all vessels the importance of a proper lookout by all available means including radar. Proper use of radar equipment including long range scanning and radar plotting allows for early detection, assessment and warning of vessels posing a risk of collision. This allows the watchkeeper sufficient time to take early and considered action to avoid collision in accordance with the International regulations for preventing collisions at sea, 1972 (as amended) (COLREGs).
The occurrence
Overview
On the evening of 12 August 2017, the timber-hulled fishing vessel, Mako, collided with the container ship Glasgow Express, about 15 NM south of Cape Woolamai, Victoria. Both vessels had been on settled courses and speeds for at least 2 hours before the collision. Despite both crews detecting and monitoring the other vessel, both vessels maintained their respective courses until they collided.
Mako
Earlier that evening, at 2000,[1] the 14.2 m long Mako (Figure 1) departed the fishing harbour in San Remo, Victoria, for a 3 day fishing trip. On board were the skipper and one deckhand. They had provisioned and fuelled the boat earlier in the day and were planning to be at their intended fishing grounds, in Bass Strait, at about 2300. In preparation for departure, the skipper had started and checked the boat’s navigational equipment (radar, chart plotter and VHF radio) and ensured the navigation lights were operating.
Figure 1: Mako alongside in San Remo after the collision
Source: ATSB
The crew reported that as they sailed out the channel, all deck working lights and external lights were on as they set the paravanes (stabilising arms). The lights remained on as the skipper steered the vessel out to sea. At about 2030, they passed the heads at San Remo at a speed of about 6 to 6.5 knots[2] and the skipper set a course of about 210°, which he intended to keep until nearing the destination. He took the watch while the deckhand settled in and went below for a rest.
The weather was overcast with light rain showers and about 15 knot winds from the south-west. The boat was rolling moderately in seas from the south-west and sea spray occasionally passed over the deck. The spray and light rain splattered the wheelhouse windows with water droplets.
At about 2230, the skipper roused the deckhand to take the watch while he rested prior to reaching the fishing grounds. During his watch the skipper had monitored a number of ships on the boat’s radar and visually. He passed on information regarding his last sighting of a ship that he determined was passing from port to starboard, ahead and well clear of Mako. All else seemed clear. He then lay down to rest on the bunk in the wheelhouse, immediately behind the conning position, and the deckhand took over. The deckhand reported that he did not verify the sighting of the ship or its echo on the radar as he settled in for the watch.
Glasgow Express
Meanwhile, at 2000, some 40 NM to the south-east of Mako, the 281 m long Glasgow Express (Figure 2) was en route from Sydney to Melbourne. At that time, the navigation watch changed and the second mate took over as officer of the watch (OOW), assisted by an ordinary seaman as lookout. The ship was south of Cape Liptrap, with a speed of 13.5 knots, on a course of 299°, bound for the pilot boarding-ground off the entrance to Port Phillip (Figure 3). The bridge log book recorded conditions as cloudy with good visibility, with the ship working moderately in rough seas with winds at Force 6[3] (22 to 27 knots) and a sea state of 5.[4]
Figure 2: Glasgow Express
Source: Hapag-Lloyd
At 2200, the lookout left the bridge to complete routine safety rounds. The second mate reported that, at about this time, he visually identified a well-lit vessel (Mako) about 3 points[5] to starboard of the bow. He watched the target and concluded it was on a similar course as the ship, and estimated it would pass more than 1 NM to starboard as Glasgow Express overtook it.
At about 2230 the lookout returned to the bridge and reported all was well on the safety rounds. He went to his lookout position on the starboard side of the bridge and also identified the vessel to starboard. The lookout reported the sighting to the second mate and together they agreed that the vessel was ahead of them, they were overtaking it, and that it would pass well clear of the ship. They also concluded the target was a fishing boat maintaining a similar course to their own. The lookout then maintained visual observation of the target. The second mate stated he did not attempt to identify, confirm and/or track the target on the radar located adjacent to the lookout’s position.
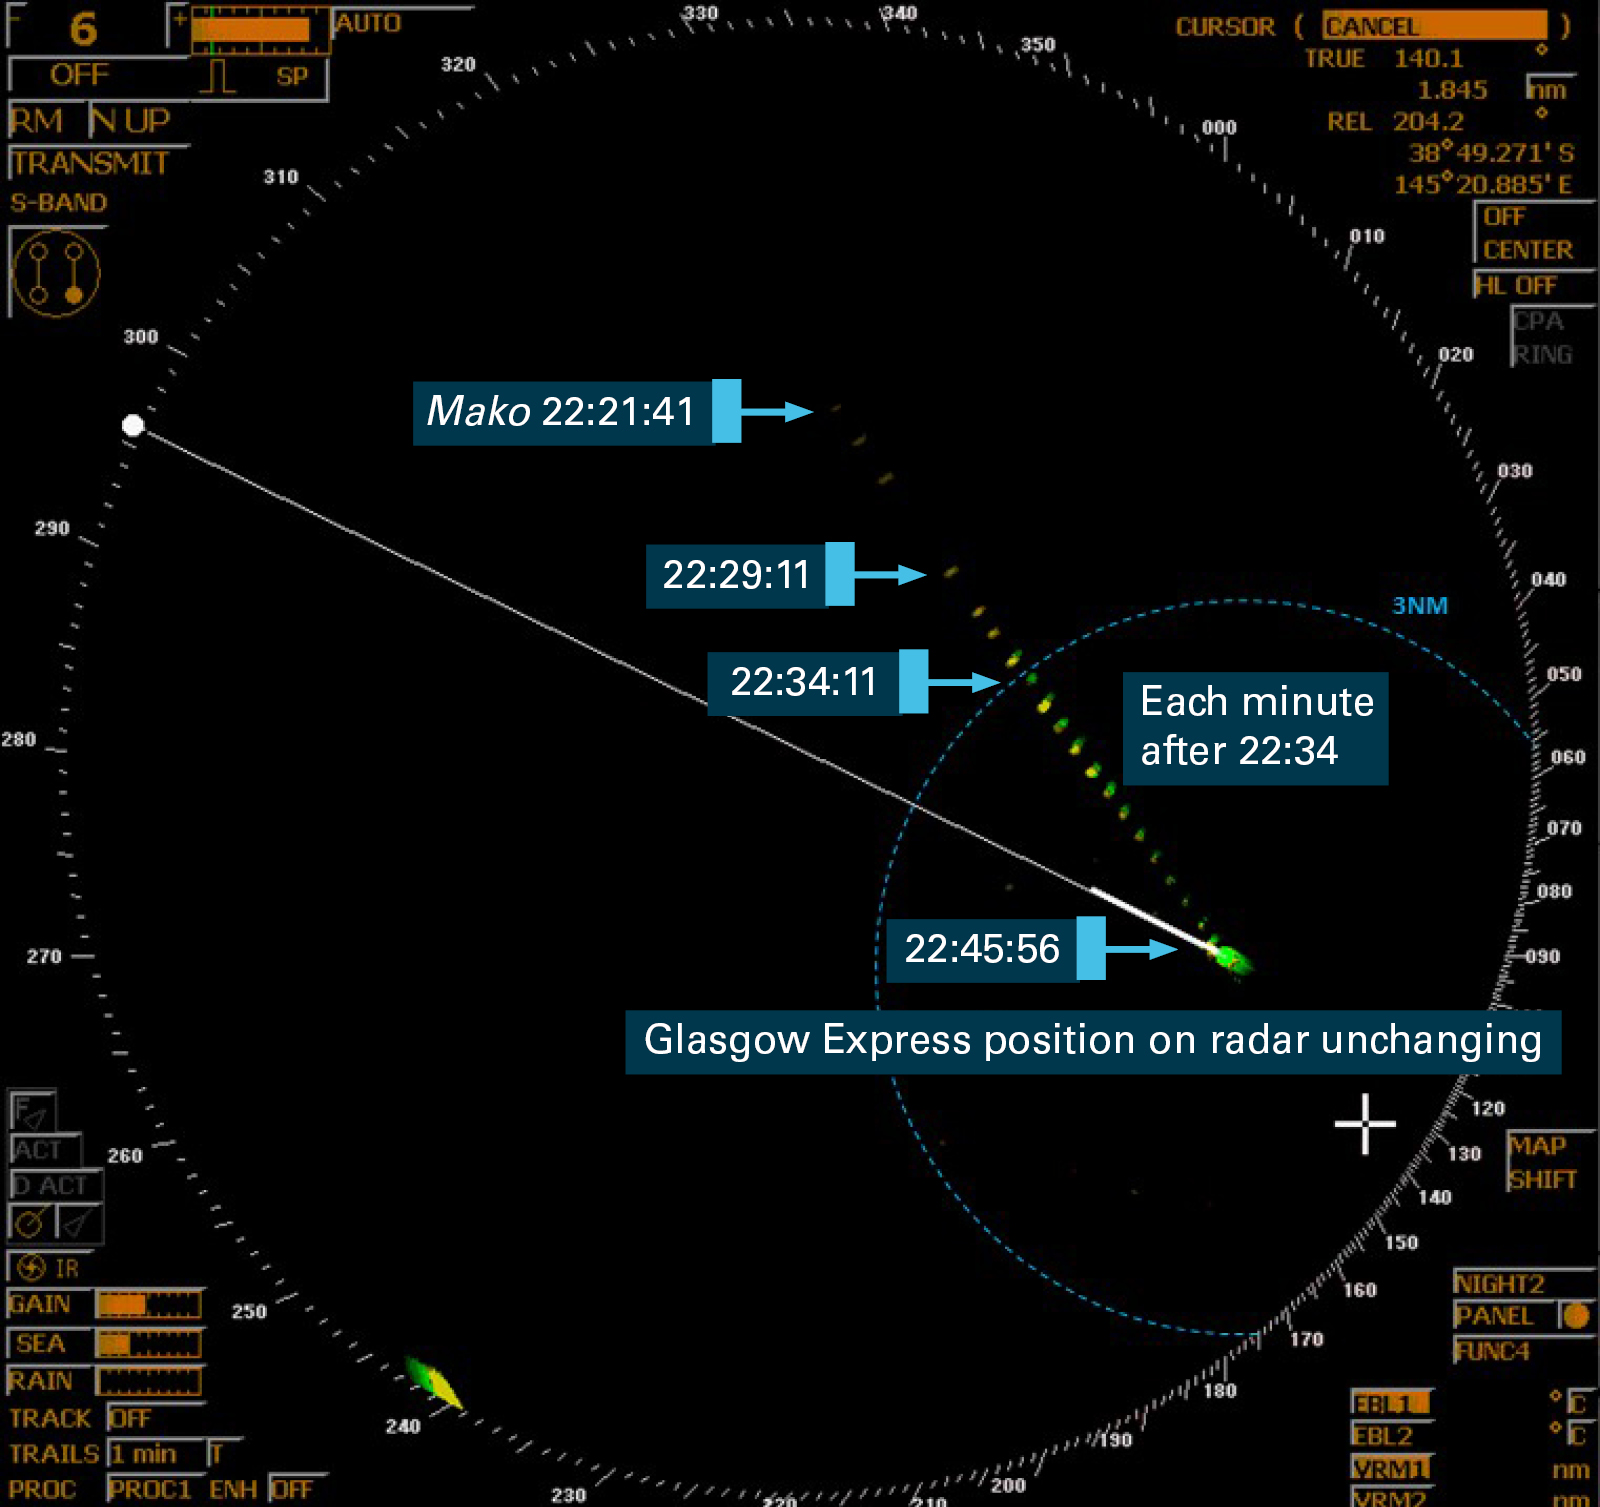
Following the collision, some data was downloaded from the Glasgow Express’s voyage data recorder (VDR). This data showed that, at 2222, an intermittent echo appeared on Glasgow Express’s S-band radar. This echo was Mako; 2.5 points to starboard and 5.5 NM from the ship. From 2232 onward, the echo would have been consistently visible on this radar.
The collision
At 2234, Mako and Glasgow Express were about 3 NM apart on converging courses. Mako’s deckhand had not observed the ship and was unaware of its presence. Glasgow Express’s bridge team continued to observe the brightly-lit Mako and to assumed that their ship would overtake and pass well clear, and to port of it. The Glasgow Express’s second mate continued to rely on visual observations for his understanding of the situation.
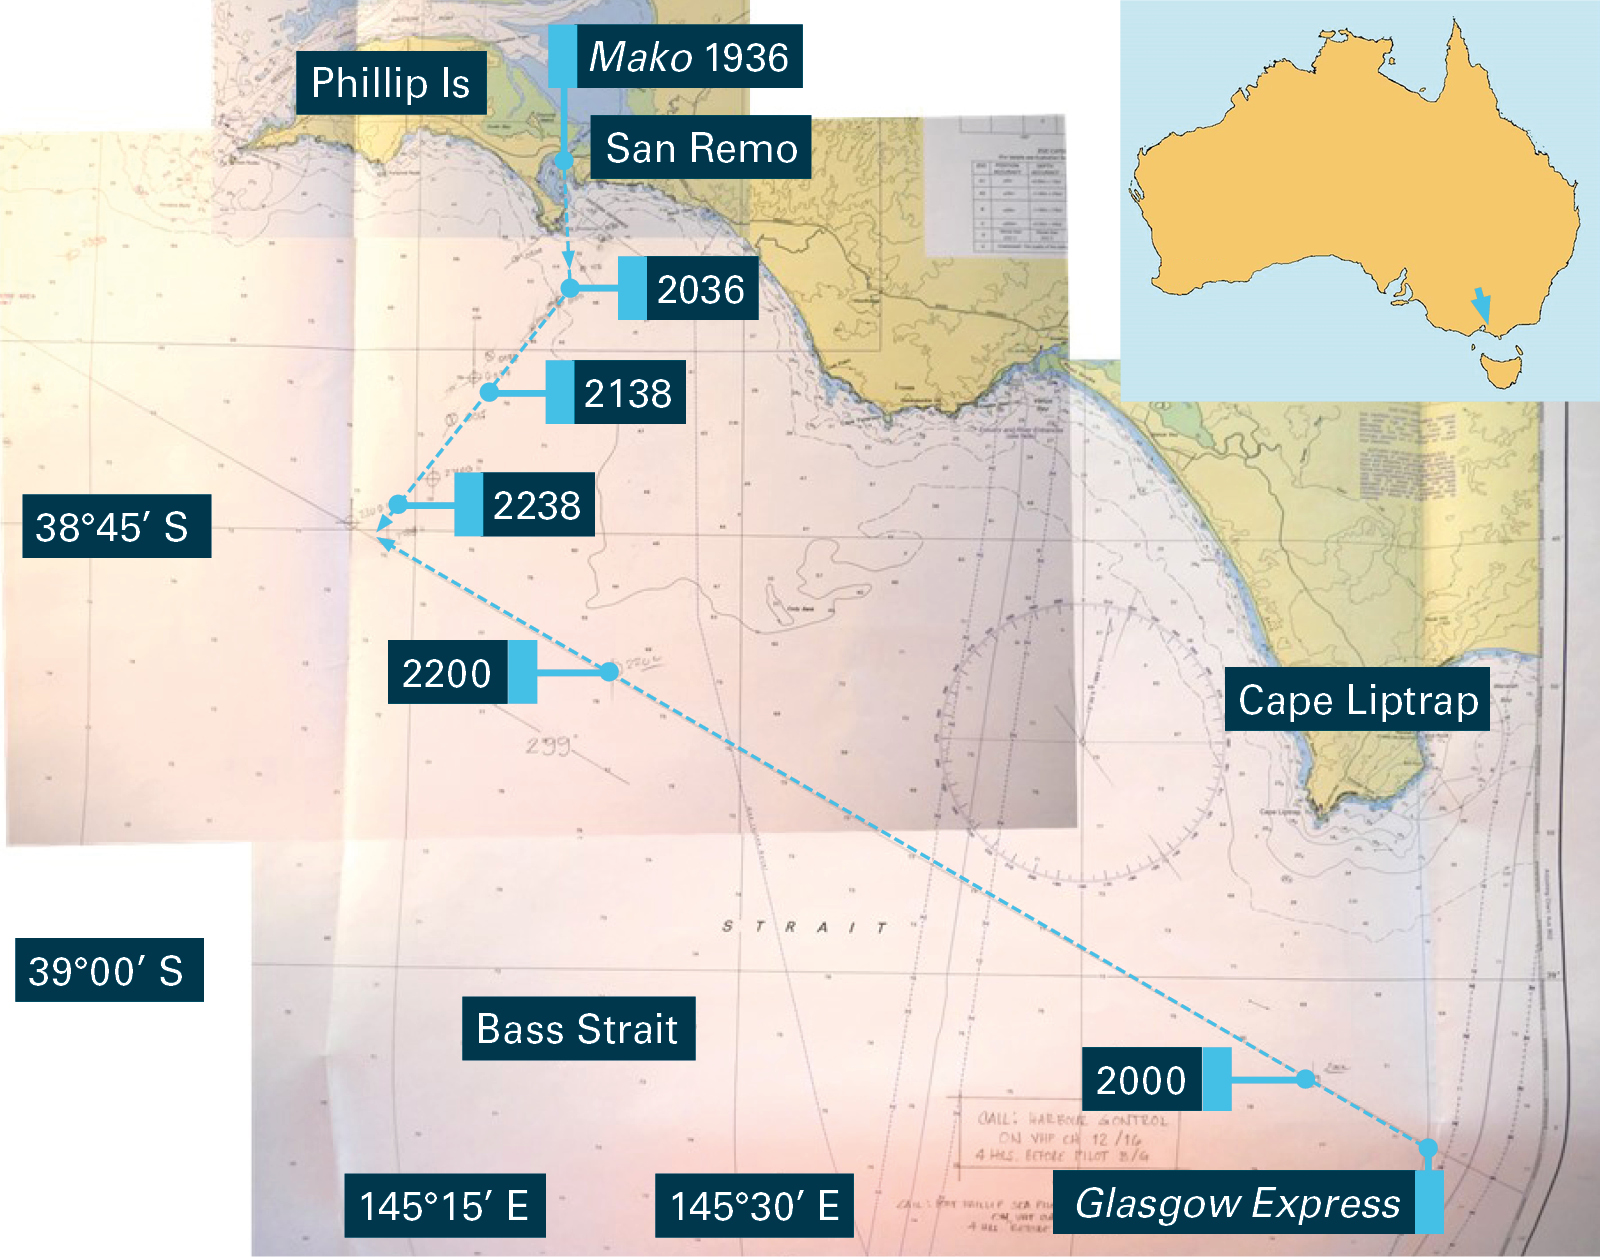
The fishing boat and the ship continued on their respective courses without change until, at 2246, in position 38° 45.5’ S 145° 13.6’ E, they collided (Figure 3).
Figure 3: Composite excerpt of Glasgow Express’s navigational chart (Aus 801) showing vessel tracks to collision
Source: Hapag-Lloyd; Australian Hydrographic Service; annotations by ATSB
Moments before the collision, Mako’s deckhand become aware of a light on the port beam, visible out the window of the portside wheelhouse door. He went to the door, shielded his eyes and looked out in time to see Glasgow Express’s bow bearing down on the fishing boat. He then saw the ship’s side and felt the impact. The skipper was immediately roused from his rest and moved the engine control lever to full astern. The boat was turned to starboard by the passing ship and the port stabiliser arm made contact with the ship’s side.
Shortly before impact, Glasgow Express’s second mate became aware of the immediate danger. He directed the lookout to take the wheel, engage hand steering and turn immediately, hard to port. At the same time, he sounded the ship’s whistle. The ship turned to port as the fishing boat contacted the hull on the starboard side in the region of cargo hold number 2—about 50 m aft of the bow.
After the collision
The fishing boat scraped down the starboard side and then passed aft of the ship. The fishing boat’s port stabiliser arm broke off and was dragged alongside by its lines. The skipper cut the stabiliser arm free and then attempted to determine the condition of the deckhand and the boat. The deckhand was shaken but otherwise unhurt. Inspection of the bow and forecastle revealed damage to the bow but no ingress of water.
GlasgowExpress continued to turn to port and slowed. The second mate called the master to report the collision and the master, who had been asleep in his cabin, hurried to the bridge. As the ship continued to turn, the second mate called Mako on the radio seeking information and offering assistance.
Over the following minutes the situation calmed. Radio contact continued between the ship’s master and the fishing boat skipper and shore authorities were alerted to the incident. The Australian Volunteer Coast Guard station at Hastings was alerted and activated its rescue boat to go to Mako’s assistance.
The ship’s master confirmed the condition of the fishing boat and crew and kept Glasgow Express standing by. The ship then escorted Mako back toward San Remo and the approaching coast guard boat. At 0130 on 13 August, Mako was taken under escort by the coast guard rescue boat and Glasgow Express was released. At 0200, the master resumed the ship’s passage toward Melbourne.
Mako was escorted to San Remo and at about 0300 was safely alongside.
Figure 4: Composite representative image showing the scale and approximate point of collision
Source: Hapag-Lloyd; ATSB
Damage
Mako suffered significant damage from the collision. The stem post was broken and the forecastle space was opened to the outside (Figure 5). However, the boat had remained otherwise watertight and did not take on any water. In addition, about 1 m of the bow was stoved in, the sheer strake[6] was marked and scratched for several metres along the port side, and the port stabiliser arm had broken away and the stabiliser arm mounting structure, including the boat’s main mast, had been pushed to starboard.
Figure 5: Damage to Mako
Source: ATSB
Glasgow Express was inspected while alongside in Melbourne. Scratch marks from Mako’s stabiliser arm were visible from the impact point, about 50 m aft of the bow on the starboard side, to the stern (Figure 6). No other damage was found.
Figure 6: Scratches along the side of Glasgow Express
The container ship Glasgow Express and the fishing vessel Mako collided at about 2246 on 12 August 2017. At the time the vessels were about 15 NM south of Cape Woolamai, Victoria. Both vessels had been settled on course and speed for at least 2 hours before the collision.
This analysis will examine the incident, collision avoidance requirements and the relationship to the lookouts kept on both vessels. It will also assess the relevance of automatic identification systems (AIS) and voyage data recorders (VDR) to this incident.
The collision
At 2036, Mako was settled on a course of about 210° at a speed of about 6 knots. At the same time, 31 NM to the south-east, Glasgow Express was settled on a course of 299° at a speed of 12 knots. From this point the two vessels were on a collision course unless some avoiding action was taken.
Glasgow Express’s officer of the watch (OOW) first sighted Mako at about 2200. Together, the OOW and the lookout mistakenly interpreted the visual information and agreed that they were overtaking the fishing vessel. No action was taken to use any other bridge equipment to confirm the actual situation, despite Mako being visible on the S-band radar intermittently from 2222, and continuously from 2232 (Figure 7).
On board Mako, visual and radar information was also misinterpreted, and it was assumed that Glasgow Express was passing well clear and ahead of the fishing vessel. As a consequence, the risk of collision was not identified and no avoiding action was taken.
At 2234 the two vessels were 3 NM apart and clearly visible to each other. However, the risk of collision was not identified on either vessel. As a consequence, no avoiding action was taken until the collision occurred 12 minutes later.
Figure 7: Glasgow Express's S-band radar image at 22:21:41 with the progress of Mako overlaid to the time of the collision
Source: Hapag-Lloyd with annotations by ATSB
Lookout and collision avoidance
Industry requirements and guidance
The International regulations for preventing collisions at sea, 1972 (as amended) (COLREGs) apply to all vessels at sea, including fishing vessels. The COLREGs require every vessel to maintain a proper lookout by ‘all available means’ so as to be able to make a full appraisal of the situation and to determine the risk of collision.
Specific mention is made in the regulations of the proper use of radar equipment to obtain early warning of the risk of collision. The regulations also warn against making assumptions based on scant information.
In addition, the COLREGs advise, among other things, that the risk of collision:
…shall be deemed to exist if the compass bearing of an approaching vessel does not appreciably change…
Other guidance and regulations[7] require that masters and all persons engaged in watchkeeping duties observe the standards and guidance regarding watchkeeping set out in Sections A-VIII/2 and B-VIII/2 of the International Convention of Training, Certification and Watchkeeping for Seafarers (STCW code).[8] The STCW code states that the officer in charge of the navigational watch is the master’s representative and is primarily responsible at all times for the safe navigation of the ship and for complying with the COLREGs.
STCW guidance on the principles to be observed in keeping a navigational watch require that:
a proper lookout must be maintained at all times
using all available means
fully appraising the situation and the risk of collision
in compliance with the COLREGs.
In performing a navigational watch, the STCW code requires that the OOW, among other things:
shall take frequent and accurate compass bearings of approaching vessels as a means of early detection of risk of collision
take early and positive action to avoid collision and ensure the actions are effective
use radar in compliance with the COLREGs
ensure that radar echoes are detected as early as possible
ensure that plotting and/or systematic analysis of radar echoes is commenced in ample time.
With regard to interaction between vessels, the COLREGs also state that any vessel overtaking any other shall keep out of the way of the vessel being overtaken. Furthermore, in a crossing situation where a risk of collision exists, the vessel which has the other vessel on its starboard side shall keep out of the way of that other vessel and shall as far as possible avoid crossing ahead of it.
Glasgow Express
The operator of Glasgow Express, Hapag-Lloyd Ship Management, has established and introduced a Safety Management (and Environmental Protection) System (SMS) throughout its fleet in accordance with the ISM Code.[9] This structured and documented system, in the form of a Safety Management Manual comprising the ISM Main Manual and ISM Emergency Plans, enables company personnel to effectively implement company policy.
The SMS includes guidance and procedures in relation to the navigation of the ship and maintaining a navigational watch. These procedures provide general guidelines for proper performance of the navigational watch, with reference to applicable and relevant rules, regulations and industry guidance. In particular, the SMS procedures require that at all times ships need to be navigated in compliance with the COLREGs, the master’s standing orders, and the STCW Code, as well as the knowledge and application of the guidance contained in the Bridge Procedures Guide.[10]
Glasgow Express’s OOW sighted the brightly-lit Mako at about 2200, at a distance of 11 NM. From that point, the OOW, and later the lookout, visually monitored it. They concluded, from their observations, that they were overtaking the fishing vessel, and believed the white lights were directed toward the stern of the fishing vessel and that one of them was its sternlight. Although the bright lights made Mako easily visible, initially this was at a distance significantly beyond that which its navigation lights are required to be visible (2 NM for sidelights and sternlight).[11]
As the vessels closed on each other, the bright decklights would have acted to obscure Mako’s navigation lights. In addition, the sidelights were positioned aft and inboard of Mako’s stabilising arms. In a seaway, these arms would have intermittently obscured the sidelight. To the observers on Glasgow Express, this would have made an accurate and complete appraisal of the situation, such as Mako’s heading, difficult based only on the vessel’s lights.
Having visually identified the presence of Mako, the OOW should then have made attempts to verify this target using other equipment, in particular the radar, and by monitoring its bearing over time. However, the OOW did not seek further information to confirm the visual sighting, including that he was seeing the fishing boat’s sternlight. A full appraisal of the situation using ‘all available means’ was therefore not made. Discussion between the OOW and lookout merely resulted in confirmation of the incorrect assumptions they had made.
Had the situation been confirmed by radar or by any other means, the overtaking scenario would quickly have been exposed as false. Confirmation by these means would have made it clear that the two vessels were in a crossing situation, with Glasgow Express as the give-way vessel. Regardless, the regulations required both the give-way vessel and the overtaking vessel—which Glasgow Express assumed that it was—to keep out of the way of the other vessel.
Furthermore, Figure 7 shows that for at least 25 minutes before the collision, Mako maintained an unchanging bearing in relation to Glasgow Express. As stated in the COLREGs, this is indicative of a collision situation. Glasgow Express’s OOW reported that he recalled first seeing the lights of Mako at about 2200. Mako’s bearing would have remained unchanged from this point. Therefore, there were more than 45 minutes in which the situation could have been clarified.
Notwithstanding this, the radar in operation on Glasgow Express was not set up to automatically acquire and track targets, in accordance with the practice of good seamanship. It is also usual practice to set up a radar guard zone, to provide warning of any target approaching within the minimum safe passing distance. Had this been done, an audible and visual alarm would have sounded as soon as the radar detected that the target, Mako, was on a collision course.
A proper lookout by ‘all available means’, as required by company and ship procedures, the master’s expectation and the regulations was not maintained on board Glasgow Express. Had the visual information, and the unchanging bearing of the target, been confirmed using radar, the risk of collision would have been clear. Effective avoiding action could have then been taken in time to prevent a collision.
Mako
As Mako departed San Remo, the skipper was aware that there was shipping traffic in the area through which Mako would pass. He set the radar and monitored a number of vessels both on the radar and visually. After the incident, the skipper recalled that he had seen a ship passing ahead and across Mako from port before he roused the deckhand to take the watch. He said he could see this ship’s starboard navigation light and concluded it would pass well clear of Mako. He passed this information on to the deckhand during handover at about 2230. The deckhand did not verify this sighting, or its echo, on the radar as he settled in for the watch.
Ship traffic information from AIS data and from Glasgow Express’s radar images show that there was a number of ships in the area on the evening of 12 August. However, after about 2100, the only ship passing port to starboard near Mako was Glasgow Express. It is likely, then, that the ship Mako’s skipper recalled observing was Glasgow Express. He had misinterpreted the situation and the danger posed by Glasgow Express when assuming it would pass clear.
Furthermore, Mako had all its decklights on throughout its voyage. Under the COLREGs, fishing vessels are not entitled to do this, and should have only their navigation lights on, unless actually ‘engaged in fishing’.[12] These bright floodlights served to reduce the effectiveness of Mako’s watchkeeper’s night vision and thus the ability to distinguish features beyond the glare of the lights. This was exacerbated by sea spray and light rain obscuring the windows. This reduced the likelihood that Mako’s watchkeeper would have visually identified the presence of Glasgow Express.
In addition, many fishing vessels are constructed with the working deck located forward of the wheelhouse. Some, such as Mako, are also fitted with fishing net winch drums on the working deck. These winch drums can be of substantial size and, as a result, create blind sectors and obscure the view forward from the wheelhouse (Figure 8). Current regulations[13] (available at www.amsa.gov.au) limit the extent of such obstructions. However, these regulations have not been applied retrospectively and consequently, older vessels, such as Mako, continue to have equipment mounted on the foredeck obscuring the field of vision from within the wheelhouse.
Large equipment mounted on the foredeck presents as a significant risk to maintaining a proper lookout by watchkeepers. However, in this case, given the relative bearing of the Glasgow Express, it is unlikely that the winch drum significantly affected the ability of Mako’s watchkeeper to detect the other vessel. Nevertheless, it is important that this limitation in vessel design is recognised and understood by fishing boat crews in order to account for blind sectors and prevent future collisions.
Figure 8: View from the conning position in Mako’s wheelhouse
Source: ATSB
In summary, Mako was brightly lit in contravention of the COLREGs and a proper lookout as required by the COLREGs and prudent seamanship was not being maintained. Misinterpretation of radar information and limitations posed by the glare from the decklights combined with other factors led to Glasgow Express not being identified as a collision risk. As a consequence, no avoiding action was taken.
Navigation equipment requirements for domestic commercial vessels
The Australian Maritime Safety Authority (AMSA) is responsible for the safety of vessels and the seafarers who are operating in the domestic commercial industry. At the time of the collision, Mako was in survey with AMSA as a Class 3B domestic commercial vessel (DCV). Under current legislation, Class 3B vessels are required to carry an AIS Class B receiver/transmitter unit. However, grandfathering of survey arrangements for older DCVs (built before July 2013) allows them to continue to operate under the survey requirements that existed before the introduction of the national standards. Built in 1980, Mako was not required to have an AIS unit fitted to comply with survey requirements, and an AIS unit was not fitted on Mako at the time of the collision.
AIS is a VHF radio broadcasting system that transfers packets of data including course, speed and other pertinent vessel details. The system enables AIS-equipped vessels and shore-based AIS stations to send and/or receive identification information that can be displayed on an electronic chart, computer display, compatible radar or standalone unit. In this way, the information received can provide the navigational watchkeeper with immediate information regarding traffic in the area. This information can then be used as part of the all available means to assist the watchkeeper in making a full appraisal of the situation and of the risk of collision.[14]
Had Mako been fitted with and used an AIS transceiver, and depending on how the equipment was configured, the watchkeeper could have been alerted to the presence of Glasgow Express on 12 August. This information could then have been used to correctly appraise the situation and the taking of necessary action to avoid a collision. For this reason, it would be prudent for older vessels, such as Mako, to carry and use this equipment.
Glasgow Express was fitted with an AIS Class A receiver/transmitter unit, as required by SOLAS.[15] Had Mako carried and been using an AIS this would have been detected by equipment on Glasgow Express. The ship’s radar could have automatically acquired and tracked Mako, triggering alarms if the vessel was to approach too closely, within a prescribed distance. The risk of collision would then have been readily apparent to the OOW and appropriate action could have been taken.
That said, the actions of Glasgow Express’s OOW, and the VDR recording, show that the ship’s radars were not set up to acquire and track AIS targets. It is, therefore, likely that even if Mako had been carrying an AIS, it would have made little difference to the actions on board Glasgow Express.
Previous collisions between ships and small vessels
The ATSB has been concerned about the number of collisions between trading ships and small vessels for many years. From 1990 to 2017, 63 collisions between trading ships and small vessels (excluding attending tugs) were reported to the ATSB or its predecessor. Of these, 38 were investigated. These safety investigations have consistently shown that keeping a proper and effective lookout and taking early avoiding action in accordance with the COLREGS could have prevented those collisions in almost every instance.
In a 2014 safety investigation report,[16] the ATSB issued a Safety Advisory Notice (MO-2014-006-SAN-019) to industry, which stated:
The Australian Transport Safety Bureau reinforces to masters, owners, operators and skippers of all vessels, the importance of taking all necessary measures to ensure that a proper and effective lookout, in accordance with the collision regulations, is kept at all times and early avoiding action in accordance with those regulations is taken to prevent collision.
Unfortunately, these types of collisions are still occurring. While measures to prevent collisions might appear straightforward, the recurrent contributing factors in collisions between ships and small vessels indicate that further effort is required from operators and crews to implement such measures.
Human performance aspects that are relevant to some of these collisions include expectancy and confirmation bias. Expectations are based on past experience and other sources of information, and they strongly influence where a person will search for information, what they will search for and their ability to notice and recognise a target or relevant aspect of a situation (Wickens and McCarley 2008). If the expectations are incorrect, then a person will be less likely to detect the target or a relevant aspect of the target (such as the heading or speed).
People generally seek information that confirms or supports their hypotheses or beliefs, and either discount or do not seek information that contradicts those hypotheses or beliefs. When the available information is ambiguous, it will generally be interpreted as supporting the hypothesis. This confirmation bias is an inherent aspect of human decision-making and has been demonstrated to occur in a wide range of contexts (Wickens and Hollands 2000).
If an assessment of another vessel’s heading and speed is based on limited or incomplete information, there is a significant likelihood it will be incorrect. However, aspects such as expectancy and confirmation bias mean an initial incorrect assessment may not be effectively identified and corrected. Accordingly, it is imperative that crews follow the relevant requirements and guidance, and use all available means when looking out for, and then monitoring, other vessels.
Small vessels can improve their detectability with aids such as AIS transceivers and radar reflectors. An AIS transceiver can also assist small vessel crews in the early detection of ships and provide important dynamic and static ship information.
For ships, allowance must always be made for crew errors, and systems must be robust enough to detect errors or omissions before an accident results. Configuring the ship’s radar to automatically acquire and track other vessels fitted with AIS and triggering alarms if the vessel was to approach too closely is one solution currently available to compensate for human fallibility.
In addition to many previous ATSB investigation reports, a number of ATSB safety bulletins also highlight collision risks to educate seafarers and mariners. These documents and other safety information about marine safety issues are available on the ATSB website.
Voyage data recorder data and recovery
All ships of 3,000 gross tonnage or more, constructed on or after 1 July 2002, are required to carry a VDR to assist with accident investigation. Glasgow Express was fitted with a Simplified Voyage Data Recorder (S-VDR). The S-VDR consisted of the final recording medium contained in the protective capsule, which held at least 12 hours of data, and a removable compact flash memory card, which could be preserved by the crew following an incident.
Glasgow Express’s crew initiated the save procedure following the collision on 12 August 2017, and removed the compact flash memory card from the system. The S-VDR continued in an operational state, with data on the protective capsule being overwritten. However, the compact flash memory card installed at the time the save function was initiated was not of sufficient size to record the previous 12 hours of data.
Upon ATSB investigators attending the vessel the data loss was identified, and a subsequent review and download of the data contained within the protective capsule was performed. Radar images and parametric data at the time of the incident were able to be retrieved, however, the bridge audio data had already been overwritten.
In addition to providing beneficial information to investigations following an incident or accident, appropriate use of the data recorded on VDRs can be of value to operators for such things as analysing vessel performance. Further, routine download of data by crews would ensure they are familiar with the operation and requirements of the system fitted to the vessel. This would then allow for effective recovery of data in the case of an incident or accident.
From the evidence available, the following findings are made with respect to the collision between the container ship Glasgow Express and the fishing vessel Mako on 12 August 2017 about 15 NM south of Phillip Island, Victoria. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Contributing factors
A proper lookout using ‘all available means’ was not maintained on board Glasgow Express. In particular, radar was not used and the relative bearing of the other vessel was not monitored over time.
A proper lookout was not maintained on board Mako. In particular, radar was not effectively used, and little if any visual sightings were conducted after it was (incorrectly) assessed that Glasgow Express was passing clear.
Mako was operating with all decklights on while under way. Although the bright lights increased the ability of Glasgow Express’s crew to detect the presence of the vessel, they also made it more difficult to determine its navigation lights and accurately and completely appraise the situation. In addition, glare from the lights likely made it more difficult for the crew of Mako to visually detect the presence of other vessels.
Other factors that increased risk
Mako did not have an Automatic Identification System (AIS) transceiver fitted, nor was such a unit required to be fitted because of the age of the vessel. Had an AIS been carried, the presence of Glasgow Express could have been alerted to Mako’s crew. In addition, relevant information about Mako, such as heading and speed, would have been available to the bridge team on Glasgow Express.
As with many other fishing vessels, Mako had a fishing reel mounted forward of the wheelhouse, which significantly obstructed the watchkeeper’s ability to maintain a visual lookout forward. This increased the risk of objects not being detected and therefore of collision.
Other key findings
Glasgow Express was fitted with a voyage data recorder, and the crew attempted to download the data following the collision. However, due to the use of an undersized memory card, not all of the available information was able to be effectively downloaded and made available to the safety investigation.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Hapag-Lloyd Ship Management
Hapag-Lloyd Ship Management, Glasgow Express’s operator, notified the ATSB that the incident had prompted a fleet-wide information program outlining details of the incident. The program emphasised that the officer of the watch was responsible for ensuring safe navigation at all times in accordance with collision regulations and using all available means.
In addition to this, voyage data recorder annual performance test procedures were amended to include ensuring the correct memory card is fitted.
Sources and submissions
Sources of information
The sources of information during the investigation included:
the master and watchkeepers of Glasgow Express
the owner, skipper and deckhand of FV Mako
Hapag-Lloyd (operator of Glasgow Express)
the Australian Maritime Safety Authority (AMSA)
the Australian Volunteer Coast Guard
the Federal Bureau of Marine Casualty Investigation (BSU), Germany
Marine and Safety Tasmania (MaST)
Maritime Safety Victoria.
References
Australian Maritime Safety Authority 2013, Information for Seafarers regarding Watchkeeping Standards, AMSA, Canberra. Available at www.amsa.gov.au.
Australian Maritime Safety Authority 2015, Marine Order 28 (Operating standards and procedures) 2015, AMSA, Canberra. Available at www.amsa.gov.au.
Australian Maritime Safety Authority 2016, National Standards for Domestic Commercial Vessels,Part C Design and construction, Section 1 Arrangement, accommodation and personal safety, AMSA, Canberra. Available at www.amsa.gov.au.
International Chamber of Shipping 2016, Bridge Procedures Guide, Marisec Publications, London.
International Maritime Organisation, The International Convention for the Safety of Life atSea (SOLAS) 1974 as amended, IMO, London.
International Maritime Organisation, The International Convention on Standards of Training, Certification and Watchkeeping for Seafarers (STCW), 1978, as amended, IMO, London.
International Maritime Organisation, 1995, International Management Code for the Safe Operation of Ships and for Pollution Prevention (ISM Code) as amended, IMO, London.
International Maritime Organisation, 1995, Seafarer’s Training, Certification and Watchkeeping (STCW) Code, 1995, as amended, IMO, London.
International Maritime Organisation, 1997, Resolution A.861(20) Performance Standards for Shipborne Voyage Data Recorders, IMO, London.
International Maritime Organisation, 2004, Resolution MSC.163(78) Performance Standards for Shipborne Simplified Voyage Data Recorders (S-VDRs), IMO, London.
International Maritime Organisation, 2006, Resolution MSC.214(81) Adoption of Amendments to the Performance Standards for Shipborne Voyage Data Recorders (VDRs) (Resolution A.861(20)) and Performance Standards for Shipborne Simplified Voyage Data Recorders (S-VDRs), IMO, London.
International Maritime Organisation 2012, MSC.333(90) Adoption of Revised Performance Standards for Shipborne Voyage Data Recorders (VDRs), IMO, London. Available at: http://www.imo.org/en/KnowledgeCentre/
Lee WU, Parker J 2007, Managing Collision Avoidance at Sea, The Nautical Institute, London.
The United Kingdom Hydrographic Office (UKHO), 2004, The Mariner’s Handbook, 8th edn, UKHO, Taunton, England.
Wickens CD & Hollands JG, 2000, Engineering psychology and human performance, 3rd edition, Prentice-Hall International Upper Saddle River, NJ.
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the master and watchkeepers of Glasgow Express, the owner, skipper and deckhand of FV Mako, Hapag-Lloyd, the Australian Maritime Safety Authority (AMSA), the Federal Bureau of Marine Casualty Investigation (BSU), Germany and Marine and Safety Tasmania (MaST).
Submissions were received from AMSA and Hapag-Lloyd. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Occurrence summary
Investigation number
333-MO-2017-007
Occurrence date
12/08/2017
Location
About 15 NM south of Cape Woolamai in the Bass Strait
On 15 August 2017, the pilot of a Robinson R44 helicopter, registered VH-HBV (HBV), conducted a private ferry flight from Cooktown to Mossman, Queensland. After refuelling in Mossman, the helicopter departed for a short ferry flight to Julatten, Queensland. The pilot was the sole occupant of the helicopter.
At about 1520 Eastern Standard Time,[1] the helicopter approached the landing site in a northerly direction. The pilot conducted an orbit at about 300–500 ft above the site to assess the conditions and then commenced the approach.
Just prior to touchdown, the pilot pulled back on the cyclic.[2] As a result, the tail rotor struck the ground behind the helicopter. The pilot felt the tail contact the ground through the airframe and pedals. The helicopter shuddered violently and yawed[3] rapidly to the right.
As the helicopter completed a 360 degree turn with the skids about 3–5 ft above the ground, the pilot lowered the collective[4] in an attempt to land on the helipad. The helicopter was still yawing as the skids contacted the helipad. It rolled over, the main rotor blades struck the ground and the helicopter came to rest on its left side.
The pilot was uninjured, and the helicopter sustained substantial damage (Figure 1).
Figure 1: Accident site showing damage to VH-HBV
Source: CASA
Pilot comments
The pilot commented that there were trees along the approach to the landing site, but it did not require a steep approach path and consequently he conducted a shallow approach. The wind at the time was from the south-east at 10 to 15 kt, but, due to the sheltered location, there was no wind at the landing site.
A company helicopter had landed shortly before HBV, and was parked on the front of the pad. The pilot commented that he may have looked at that helicopter as he touched down, which led to pulling back on the cyclic. HBV was an older model R44 helicopter than the pilot had flown previously and he reported that when the cyclic was in the neutral position, it sat slightly further forward than he was accustomed to. The pilot also commented that had he rolled off the throttle immediately after the tail rotor struck the ground, it would have reduced the helicopter’s rate of rotation and potentially prevented the rollover. He stated, however, that he did not recognise the developing situation, and roll off the throttle, before the helicopter began yawing. He also reported being unable to land the helicopter until it had rotated through 360° due to concern about terrain contact. Finally, the pilot recalled that he rolled off the throttle upon lowering the collective but the yaw did not stop completely prior to the skids contacting the ground.
The chief pilot, who witnessed the accident, indicated that the helicopter came in with the tail a bit lower than normal, the tail rotor struck a small mound of dirt, and the tail rotor and gear box detached. He commented that the pilot only weighed about 65 to 70 kg and, without any passengers or gear on board, the centre of gravity of the R44 is quite aft and the tail is therefore lower than when more heavily loaded. He further stated that the fuel tank was about three-quarters full, and the helicopter was within weight and balance limitations.
Safety analysis
The pilot applied aft cyclic just prior to touchdown, which resulted in a slightly tail-low attitude for landing. The tail stinger would normally contact the ground and prevent a tail rotor strike. However, because the ground sloped away behind the concrete landing pad, the stinger was over the slope, allowing the tail rotor to strike the ground and detach without prior warning (Figure 2).
Following separation of the tail rotor and gearbox, the helicopter yawed rapidly to the right through 360° in response to the torque associated with the still‑powered main rotor. As the pilot did not roll the throttle off quickly enough to reduce the rate of yaw of the helicopter prior to lowering the collective, the helicopter was still yawing when the skids contacted the ground. Consequently, it rolled over and the main rotor blades struck the ground.
Figure 2: Sloping ground away from helipad and tail rotor strike marks
Source: Queensland Police
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The pilot applied aft cyclic just prior to touchdown, resulting in a tail-low attitude.
The ground sloped downwards away from the landing pad and as a result, the tail stinger did not protect the tail rotor from ground contact.
The tail rotor struck the ground and detached, resulting in the helicopter yawing rapidly to the right. The pilot did not roll off throttle to reduce the yaw rate prior to lowering the collective, which probably led to the helicopter rolling over as the skids contacted the ground.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following safety action in response to this occurrence.
Helicopter operator
As a result of this occurrence, the helicopter operator has taken the following safety actions:
Company pilots were briefed immediately following the accident, and subsequently trained, with regard to flying alone or with very little cargo. R44s are inclined to have a nose-high attitude when light, which often results in tail and stinger encroaching too close to terrain.
The company hazard register was updated to highlight the issue and company pilots were required to read the updated register. Pilots were advised that higher flare and slower approaches can mitigate the hazard.
Company pilots were briefed regarding hazards associated with helicopter landing sites and bush landing sites with sloping terrain and any obstacle that may come into contact with tail rotor or helicopter.
Retraining of company pilots in special procedures, including the conduct of hovering autorotations was conducted between October and November 2017. The operator assessed that use of this technique would have reduced the damage to the helicopter.
Safety message
This occurrence highlights that a loss of tail rotor thrust at low speed and low height above the ground requires an immediate and correct response to maintain control of the helicopter. It is therefore important that pilots are primed for this emergency, particularly during the approach and departure phases of flight.
The United States National Transportation Safety Board Safety Alert Loss of tail rotor effectiveness in helicopters states that due to safety concerns, training for loss of tail rotor effectiveness (LTE) is rarely conducted in an actual helicopter. While this incident involved the detachment of the tail rotor rather than aerodynamic LTE, the stated pilot responses to LTE are applicable here and consistent with the manufacturer’s emergency procedures.
The US Federal Aviation Authority Advisory Circular 90-95 stated under effective recovery techniques (for LTE), that collective pitch reduction will aid in arresting yaw rate but may cause an increase in the rate of descent. If the rotation cannot be stopped and ground contact is imminent, an autorotation (i.e. rolling off throttle) may be the best course of action. While the pilot’s action in lowering the collective during this occurrence may have reduced the yaw rate, following the manufacturer’s emergency procedure for a loss of tail rotor thrust during hover will provide the best outcome when close to the ground. That is, if uncommanded yaw is experienced that cannot be stopped by application of opposing tail rotor pedal:
fully roll off the throttle and allow the helicopter to settle while controlling any drift
raise the collective just before touchdown to cushion the landing.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
At about 1615 Eastern Standard Time (EST), on 8 August 2017, the Aerodrome Reporting Officer (ARO) of Middlemount Airport, Queensland, inspected the runway prior to the arrival of two aircraft. The ARO found no abnormalities with the runway or runway lighting.
The first aircraft was an Embraer EMB-135LR, registered VH-JGB, operated by JetGo Australia as a charter flight from Brisbane, Queensland. On board the aircraft was a training captain, a captain under line training, a cabin crewmember and 23 passengers.
The captain under training had recently joined the aircraft operator. This was his second flight with the operator, and first to Middlemount. The flight was also his second flight on the aircraft type, having completed aircraft type training in a simulator.
During the flight, the flight crew reviewed the company briefing package for Middlemount and noted that the runway was not equipped with visual approach slope guidance.[1]
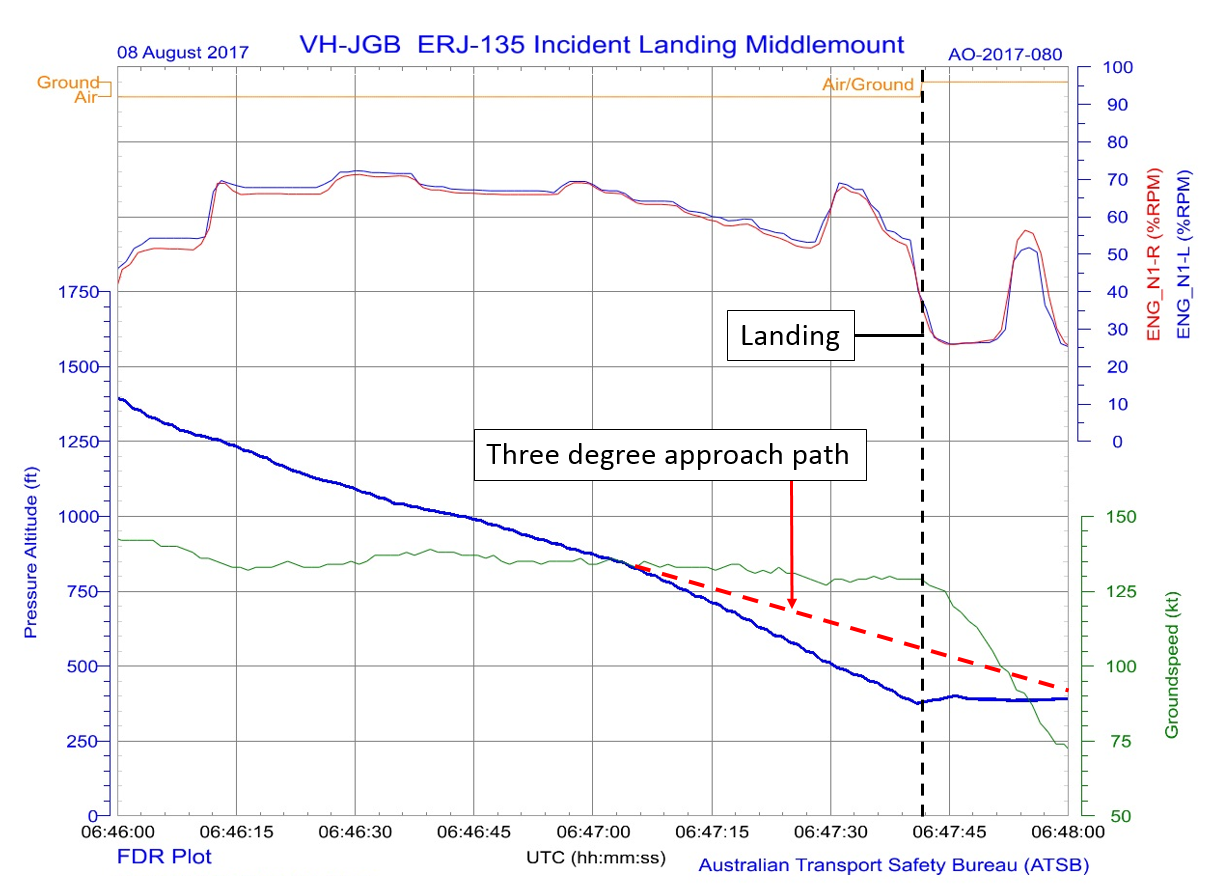
At 1643, the captain under training, acting as pilot flying,[2] positioned the aircraft on the downwind leg of the circuit for runway 11 at Middlemount. The flight crew elected to extend the downwind and final circuit legs beyond the standard length to allow the captain under training to familiarise himself with higher terrain to the north-west of the airport and radio masts in the vicinity of the runway 11 approach path. During the final approach leg, the training captain observed that the aircraft appeared to be slightly below the desired approach profile but determined that it did not require him to take corrective action.
At 1647, the aircraft landed on runway 11. The flight crew did not detect anything abnormal during the landing. The ARO observed the landing and noted that the aircraft appeared to touchdown early. The aircraft then taxied to parking normally.
A runway inspection was not carried out prior to the arrival of the second scheduled flight. The second flight arrived without incident, the ARO noted that the touchdown point for this flight appeared to be in the normal touchdown zone (Figure 1).
Figure 1: Overview of runway 11 threshold
Image shows the positions of the beginning of the runway, runway threshold lights, aiming point markers and touchdown zone. Source: Google earth, annotate by ATSB
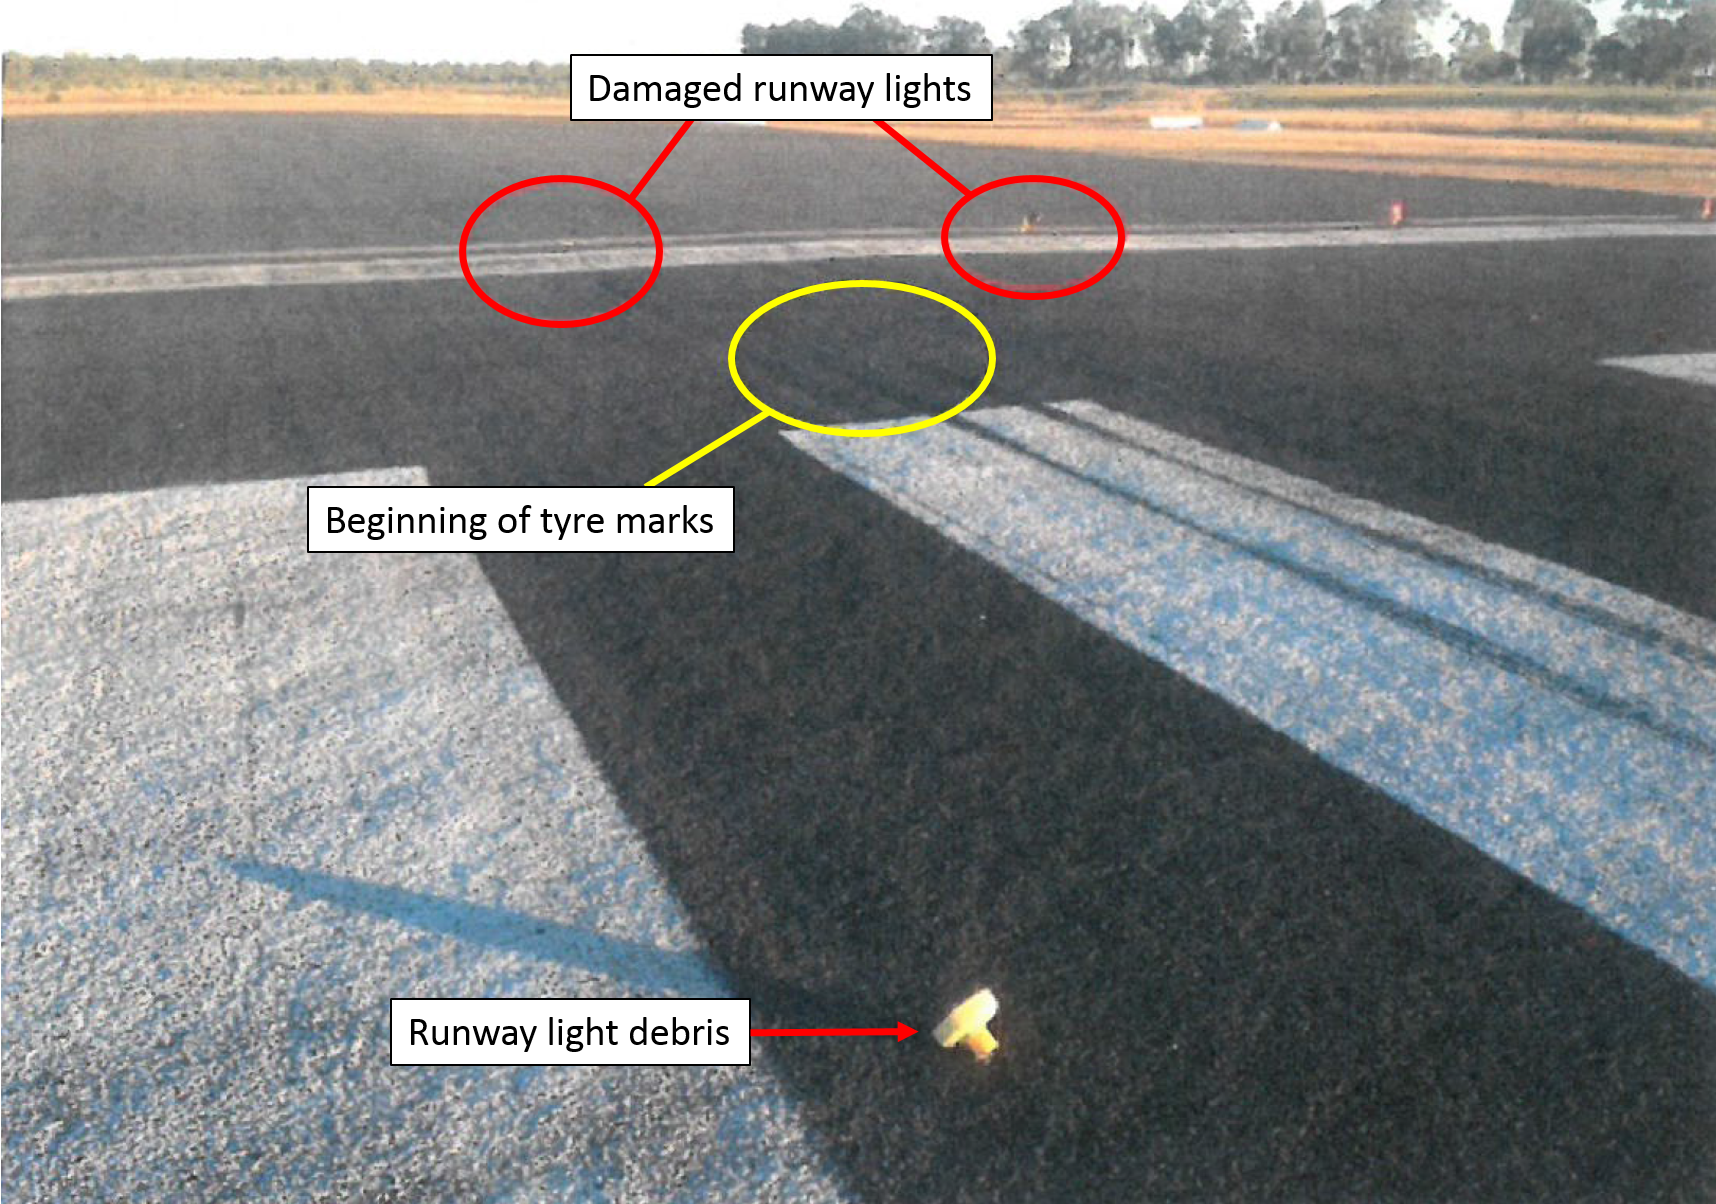
At about 1840, the ARO conducted an inspection of the runway prior to the departure of the two aircraft. During the inspection, the ARO identified two damaged runway threshold lights (Figure 2) and fresh tyre marks (Figure 3) about four meters further along the runway from the damaged lights. The ARO immediately proceeded to VH-JGB, and advised the flight crew that he believed they had damaged the runway threshold lights during their landing. The training captain inspected the aircraft tyres and landing gear and determined that the aircraft had not sustained any damage.
Figure 2: Damaged runway threshold lights
Images shows the damage to the runway threshold lights (left and centre), and a tyre mark on a damaged light (right). Source: Airport operator, annotated by ATSB
At about 1935, the ARO cleared the debris and determined the runway to be serviceable.
At 1954, VH-JGB departed runway 11 at Middlemount for Brisbane. After the aircraft arrived at Brisbane, an engineering inspection of the aircraft found no damage.
No persons were injured, and the aircraft was not damaged in the incident.
Figure 3: Runway 11 threshold
Image shows the damaged runway lights, touchdown tyre marks and runway light debris. Source: Airport operator, annotated by ATSB
Training captain comments
The training captain made the following comments:
Middlemount is the only airport the operator regularly serves which does not have visual approach slope guidance.
The selected touchdown aim point was the aiming point markers.
During the late stages of the approach, the demands of acting in the pilot monitoring role and monitoring the captain under training resulted in a very high workload.
Captain under training comments
The captain under training made the following comments:
In his previous role, the captain under training received extensive training and operational experience in conducting approaches without visual approach slope guidance. These operations were on the Beechcraft King Air 200 turboprop aircraft. He had extensive experience in jet aircraft. However, the incident flight was the first time he had conducted an approach without visual approach slope guidance in a jet aircraft.
The simulator training provided by the company included narrow runway operations and approaches without visual approach slope guidance. The captain under training also commented that he would have liked to have received more simulator training for visual approaches without slope guidance, and it would be beneficial if these types of approaches were conducted later in the line training phase.
While the approach appeared to be slightly lower than normal, as the aircraft descended through about 500 ft above ground level, the training captain called ‘stable’, indicating the approach was within tolerances. This reassured the captain under training that the approach was proceeding normally.
The demands of operating a new aircraft type, with new operating procedures, to a runway without visual approach slope guidance resulted in a very high workload during the approach.
Aerodrome reporting officer comments
The ARO made the following comments:
There was no defined procedure in place to conduct runway inspections. However, where possible, runway inspections were carried out before and after JetGo arrivals. The second flight arrived about 15 minutes after VH-JGB. The time period between the two arrivals did not allow for a runway inspection.
The ARO regularly observed JetGo arrivals and had a good understanding of the expected touchdown point.
Flight recorders
The aircraft was equipped with a flight data recorder which recorded the flight data associated with the occurrence.
Approach path
The flight data shows (Figure 4) that at 16:47:10, the aircraft was positioned on about a three-degree approach path. At this time, the descent angle increased until the aircraft flared for landing.
Figure 4: Graphical representation of recorded flight data
The data plot shows the main landing gear air/ground switch position, engine power, ground speed and pressure altitude. A representative three degree approach path and the landing are annotated. Source: ATSB
Touchdown point
The recorded touchdown point of the aircraft was consistent with the fresh tyre marks observed by the ARO.
Flight crew workload
The flight crew reported that during the approach they experienced a period of very high workload.
The flight crew also reported not detecting anything abnormal during the landing and first becoming aware of the incident when notified by the ARO.
Under conditions of stress, an individual’s attention will channel or tunnel. Focus on peripheral tasks will be reduced and centralized on to main tasks. What differentiates a main task from a peripheral task depends on what the individual perceives to be of greatest importance or greatest salience. Tunnelling of attention can result in either enhanced performance or reduced performance, depending on the nature of the task and the situation.
Aircraft operator report
The aircraft operator conducted an investigation into the incident and provided the following observations:
The flight crew felt no urgency to land the aircraft before the touchdown zone due to performance limitations. The calculated landing distance required was 1,306 m, and the landing distance available was 1,550 m.
During the landing flare, the captain under training reported having to raise his head to maintain visual contact with the runway and had difficulty in determining if the landing would be before the aim point. An incorrect seating position likely contributed to the collision with the runway lights.
Standard length downwind and final circuit legs, along with a correct seating position and corrective callouts by the training captain would have been more representative of the simulator training received by the captain under training.
Safety analysis
During final approach the aircraft descended below the final approach path, and the aircraft landed prior to the selected aim point. Prior to landing, the main landing gear tyres collided with two runway threshold lights.
This was the captain under training’s first approach without visual slope guidance in a jet aircraft. Combined with the demand of operating a new aircraft under new operating procedures, resulted in a high workload for the pilot under training during the approach. The training captain also experienced a high workload due to the demands of acting in the pilot monitoring role and monitoring the captain under training.
The high workload of the flight crew during the approach, along with the absence of approach slope guidance, likely reduced the flight crew’s ability to detect the flight path deviation.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The aircraft descended below the desired approach path and landed prior to the selected aim point. Prior to landing, the aircraft collided with two runway threshold lights.
A flight involving a captain under line training, with high workload during final approach associated with the line training, along with the absence of approach slope guidance, resulted in the flight crew not detecting that the aircraft had descended below the desired approach path.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Aircraft operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:
Changes to procedures
Landings at Middlemount will be made by captains only.
Line training flights will not operate to Middlemount.
Training for operations without approach slope guidance will be conducted as standalone training following a period of consolidation of line flying after the completion line training.
Flight crew education and training
Aircrew notices were circulated to all flight crew, providing education on operations without vertical profile guidance and Middlemount operations. The landing technique contained within the FCOM was amended to include addition information regarding runway visual illusions.
The flight crew involved in the incident underwent additional training in approaches without visual approach slope guidance prior to resuming operations to aerodromes without visual approach slope guidance.
Safety message
The ATSB has identified descending too low on approach as a risk area requiring heightened attention. When compared to other phases of flight, the approach and landing has a substantially increased workload and is traditionally the phase of flight associated with the highest accident rate. Flight crews must continuously monitor aircraft and approach parameters, and the external environment to ensure they maintain a stable approach profile and make appropriate decisions for a safe landing.
The impact of workload can be insidious, the affected individual not realising an increase until it has reached a high level. The best way of managing workload is to reduce the level of work demands and distractions. If the work demands cannot be reduced, then another option is to ensure the flight crew have the experience, skills and techniques to effectively manage their task demands. Overall, high workload can have significant effects on flight crew performance and needs to be monitored and managed using a systemic approach, particularly for less experienced flight crew, but also flight crew who have recently undertaken a new role.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 2 August 2017, the pilot of a Robinson R22 Beta II helicopter, registered VH‑HGU and operated by Cloncurry Mustering Company, departed Cloncurry Airport, Queensland, on a ferry flight in preparation for an aerial mustering operation. About 3 minutes after take-off, the pilot experienced a loss of control and the helicopter broke-up in-flight. The helicopter collided with terrain about 7 km north-north-west of Cloncurry. The pilot, who was the only occupant, was fatally injured and the helicopter was destroyed.
What the ATSB found
The ATSB found that the helicopter had recently undergone a 2,200-hour overhaul and this was the first commercial flight since that time.
The on-site examination established that the bellcrank in the helicopter cyclic control assembly was missing a fastener, which allowed the assembly to disconnect in-flight. The ATSB concluded that it was likely that the fastener’s self-locking nut was either not reinstalled or it was inadequately torqued during the overhaul. While it could not be determined what had occurred to result in this condition, it was noted that Cloncurry Air Maintenance (CAM) did not use the work-pack to record and track all maintenance activities during the overhaul, which extended over a period of almost 4 months.
The ATSB noted that, in the years leading up to the accident, the CAM workforce structure had changed in a manner that reduced the levels of its qualifications and experience. In the month leading up to the accident, the CAM workforce was operating at a very high workload, which likely exceeded their workforce capability and reduced the chief engineer's capacity to oversight maintenance activities.
Cloncurry Air Maintenance (CAM) had limited internal independent oversight of maintenance activities to evaluate its quality performance. The organisation was subject to both contracted and regulator audit activities in the years leading up to the accident. The ATSB reviewed two of the work-packs sampled during the audits and noted that discrepancies in their maintenance documentation practices were visible to the auditors. However, the auditors had not identified any issues associated with those practices, and therefore, the audits were of limited benefit to CAM.
It was also established that CAM were re-using the MS21042L-series nuts on critical fasteners without replacing them with D210-series corrosion resistant nuts in accordance with the manufacturer's instructions. However, the ATSB also found that the re-use of self-locking nuts was a common and accepted industry practice.
What's been done as a result
Cloncurry Air Maintenance have improved their maintenance practices, which has included progressive certification for tasks, adopting the helicopter manufacturer’s checklists for their inspections, removing all untracked MS-series self-locking nuts from stores, and completing inspections of the flight controls on all the Cloncurry Mustering Company helicopters with nil defects reported.
In March 2019, the Australian Transport Safety Bureau issued a safety advisory notice advising all Australian maintenance personnel for Robinson helicopters to ensure that before re-using a self‑locking nut, that the correct part number is fitted, and that the D210-series corrosion-resistant nuts are used for reassembly of critical fasteners in accordance with the Robinson Helicopter Company instructions for continued airworthiness.
As a result of this accident and other investigations by the Civil Aviation Safety Authority, the regulator issued airworthiness bulletin 67-005: Robinson Helicopter Flight Controls – Independent Inspections. The bulletin highlighted the need for independent inspections to be conducted and ‘recorded consecutively with each adjustment made during rotor tracking and balancing’ activities. In addition to several recommendations, the bulletin identified several human factor elements that could impact maintenance inspection performance, and highlighted the need for extra caution to be exercised during post-maintenance flights as per the guidance provided by Robinson.
Safety message
Although verbal communications are an important method of explaining and understanding problems, they are not a reliable means for capturing essential tasks over an extended time‑period. This accident highlights the importance for maintenance organisations to consider the human factors elements associated with their practices, capture them in their documented quality control procedures, and ensure they are complied with.
Audits are essential for independently verifying the effectiveness of an organisation's processes and procedures. This accident reinforces the importance of auditors inspecting the evidence collected during an audit to ascertain whether or not the requirements are being met, specifically conformance with the relevant standards. Audits may also be used to identify potential underlying human factors issues, which may be raised as an opportunity for improvement to inform the auditee of best industry practices.
The occurrence
On the morning of 2 August 2017, the pilot of a Robinson R22 Beta II helicopter, registered VH‑HGU and operated by the Cloncurry Mustering Company (CMC), was conducting a ferry flight from Cloncurry Airport, Queensland in preparation for an aerial mustering operation at a station to the north of Cloncurry.
The helicopter had departed from Cloncurry Airport just after first light, at about 0659 Eastern Standard Time.[1] The pilot’s colleagues reported observing the pilot warming up the engine and then take-off with a normal profile to the north. They also stated that the helicopter sounded normal on departure.
Shortly after the helicopter departed, staff from CMC and their maintenance organisation, Cloncurry Air Maintenance (CAM), observed a plume of smoke to the north. A company pilot noted that the smoke was in the general direction of VH-HGU’s track and was drifting towards the west. The pilot attempted to contact the accident pilot via mobile phone at 0713, but the call went to message bank. The company pilot departed with a colleague in another R22 towards the smoke.
The helicopter wreckage was located about 7 km north-north-west of Cloncurry Airport at about 0718 (Figure 1). The pilot was fatally injured and the on board global positioning system device indicated the accident occurred at about 0702.
Figure 1: VH-HGU accident site
Source: ATSB
On landing near the wreckage, the company pilot made a phone call to report the accident, and activated an emergency beacon to assist the emergency services with locating the site. The pilot noted there was very little soil disturbance, normally associated with main rotor blade strikes to the ground during an accident sequence. The pilot also considered the location of the accident site was consistent with the track the accident pilot would have flown to the station for the contracted work. Soon after, the emergency services arrived at the accident site and took control of the scene. The accident was not considered survivable.
Another company pilot, who departed Cloncurry just prior to the accident pilot, reported hearing no communications on the company’s mustering radio frequency. At 0702:29, an unidentified transmission occurred on the Cloncurry Airport common traffic advisory frequency. However, it was only momentary (about 1 second duration) and did not contain any voice data.
Powerline inspection
The most significant feature near the accident site was the Ernest Henry Mine high voltage powerlines, about 70 m to the west of the accident site. The first responders from CMC noted the powerlines were intact and that no other aircraft were known to be in the area at the time. Staff from the powerline company attended the site with a remotely piloted aircraft to inspect the pylons and lines. On completion of that inspection, they concluded there was no evidence of impact damage.
The pilot started flying training in 2002, and had been employed by the Cloncurry Mustering Company (CMC) since 2004, and held a Commercial Pilot Licence (Helicopter) with a flight instructor rating for low‑level helicopter operations and aerial-mustering. The pilot’s most recent flight review was on 15 November 2016 in an R22 helicopter. The pilot held a Class 1 Aviation Medical Certificate with no restrictions and an expiry date of 2 February 2018. On 6 January 2017, 10,000 flying hours experience was recorded on the pilot’s medical examination questionnaire.
On 1 August 2017, the night before the accident flight, the pilot went to bed at about 2000. The next morning, the pilot left home for work at about 0530. Several colleagues spoke with the pilot between 0600 and 0700 at the company’s hangar facility at Cloncurry Airport and reported the pilot’s demeanour as normal.
From the operator’s records, the accident occurred on the pilot’s third consecutive day of flying, which included 12.2 hours flying in the previous 2 days. Prior to that period, the pilot had not flown for 8 days. The time of the accident was not in the circadian low period and did not include an extended period of duty.
Helicopter information
General information
VH-HGU was a two-seat Robinson Helicopter Company (RHC) R22 Beta II helicopter, serial number 4335, powered by a 4-cylinder, carburettor Textron Lycoming O-360-J2A engine (Figure 2). It was manufactured in 2008 and registered in Australia in July of the same year. The helicopter was added to the CMC fleet on 16 February 2017.
Figure 2: Example R22 helicopter
Source: Queensland Police Service
Drive system
Engine power is transmitted to a V-belt sheave bolted to the engine output. The V-belts transmit power to the upper sheave, which transmits power forward to the main rotor and aft to the tail rotor. Flexible couplings[2] are located at the main gearbox input (forward flexible coupling) and at each end of the tail rotor drive shaft (intermediate and aft flexible couplings).
Rotor systems
The main rotor has two blades mounted to the main rotor hub by coning hinges.[3] The hub is mounted to the main rotor shaft by a teeter hinge. Droop stops for the main rotor blades, mounted near the top of the main rotor mast, provide a teeter hinge friction restraint, which normally prevents the rotor from teetering (rocking) while stopping or starting. Elastomeric teeter stops,[4] mounted in brackets in-line with the main rotor blades, limit the teetering during normal flight conditions and will provide a damage witness mark if there is excessive teetering of the main rotor system in-flight. The main and tail rotor systems are fitted with pitch links to transmit the flight control inputs to the rotor blades.
Flight controls
Primary controls are actuated through push-pull tubes and bellcranks. Flight control operation is conventional. The tail rotor pedals change the pitch of the tail rotor blades, and therefore the thrust, of the tail rotor system, which provides directional control. The collective[5] lever controls the amount of thrust (lift) produced by the main rotor disc. Raising or lowering the collective lever will raise or lower the swashplate,[6] which will alter the pitch on both main rotor blades to increase or decrease the main rotor thrust. The collective lever also incorporates a twist grip to provide the pilot with full manual control of the engine throttle.
The cyclic[7] control tilts the main rotor disc to point the rotor thrust in the desired direction of flight. Fore-aft movement of the cyclic provides the longitudinal (pitch) control of the main rotor disc. Forward movement will tilt it down at the front and up at the back, and aft movement will tilt it up at the front and down at the back. There is a single push-pull tube connection to the swashplate at the rear of the main rotor mast to provide the pitch control. Left-right movement of the cyclic provides lateral (roll) control of the main rotor disc. There are two push-pull tubes connected to the swashplate, either side of the main rotor mast, to tilt the disc left or right.
Recent maintenance history
The helicopter had accumulated about 4,365 hour’s total time-in-service at the time of the accident. When CMC acquired VH-HGU, in February 2017, it had about 80 hours remaining before it was due for its second 2,200-hour overhaul. Therefore, the operator’s maintenance organisation, Cloncurry Air Maintenance (CAM), completed a 100-hour inspection at the time of the acquisition and the helicopter was operated by CMC until the 2,200-hour overhaul was started on 12 April 2017.
The 2,200-hour overhaul involved the disassembly, inspections, reassembly and checks of the helicopter. All flight control push-pull tubes were sent for non-destructive testing and found serviceable. The helicopter was reassembled and a weight and balance, and fuel calibration was completed. The flight controls were rigged and then the helicopter was subject to a 100-hour inspection before a ground run, track and balance[8] of the main rotors, and autorotation RPM check were completed on 28 July 2017.
On 31 July 2017, a 15-minute local area flight was conducted to confirm the serviceability of the helicopter. Following that flight, CAM staff certified for all the tasks in the 2,200-hour overhaul work-pack, including independent inspections[9] of the engine and flight controls, and issued the maintenance release.[10]
The next time the helicopter was operated was the accident flight.
Loading and performance
The ATSB’s calculations indicated the helicopter was within the prescribed weight and balance limits for the flight. Using the local environmental conditions, the out-of-ground‑effect[11] hover performance weight was within limits at the helicopter’s certified maximum all-up-weight of 622 kg.
Meteorological information
The weather conditions recorded at Cloncurry Airport at 0700 included a wind speed of 1 kt from 100°, a temperature and dewpoint[12] of 14 °C and 5 °C respectively, and a QNH[13] of 1015 hPa. The Cloncurry aerodrome forecast[14] for the period from 0400 to 1600 included a wind speed of 6 kt from 170° and CAVOK[15] conditions. Given the insignificant conditions, the ATSB determined that it was very unlikely that the weather contributed to the circumstances of the accident.
Global positioning system data
The pilot’s Garmin GPSMAP196 navigation device was recovered from the wreckage for examination and analysis by the ATSB. The global positioning system (GPS) had several track logs, which included the accident flight and a previous mustering flight.[16]
Figure 3 depicts the helicopter’s GPS track from take-off to the accident site, and Figure 4 depicts the position of the main wreckage relative to the last reliable GPS data point and vicinity to the powerlines. Table 1 provides the data points for the accident flight. The ATSB considered the final data point (14), which was beyond the accident site, to be an unreliable point for the purpose of analysis as it very likely represented a predictive point.[17]
Figure 3: Accident flight GPS track
Source: Google Earth, annotate by the ATSB
Figure 4: Accident site datum relative to the last reliable GPS data point
Source: Google Earth, annotated by the ATSB
From Table 1, the changes in altitude and vertical speed were all positive from the departure point to the last reliable data point (13). In addition, the average ground speeds between the data points were relatively stable leading up to point 13. This suggested the helicopter had a reasonably steady climb flight profile. At point 13, the helicopter was about 279 ft above the local terrain, and about 82-148 ft above the height of the Ernest Henry powerline towers.[18]
The pilot was a patient of the Cloncurry Flinders Medical Centre since 2005, which included flight crew medical examinations by the local designated aviation medical examiner (DAME). In 2011, after a diagnosis of mild hypertension, the pilot started a prescribed daily dose of 150 mg Irbesartan.[20]
Post-mortem and toxicology results
The post-mortem examination established that the pilot received extensive injuries associated with a rapid deceleration and the cause of fatality was ruled as multiple injuries as a result of the accident. The examination also found 75 per cent eccentric stenosis[21] in the mid segment of the left anterior descending artery of the pilot’s heart. This was characterised as severe atherosclerosis.[22] The forensic pathologist reported:
It is theoretically possible that this may have precipitated abnormal heart rhythm leading to pilot incapacitation and subsequent accident. This scenario can be neither confirmed nor excluded on the basis of autopsy examination.
A low concentration of alcohol was detected in the blood, which was considered to be ‘likely post‑mortem contamination, probably due to decomposition’. No drugs, including Irbesartan, were detected.[23]
Specialist advice
In consideration of the forensic pathologist’s scenario, the ATSB conducted a follow-up on the pilot’s health with the Cloncurry DAME, the CASA Principal Medical Officer (PMO) and the Director of the Clinical Forensic Medicine Unit for the Queensland Department of Health.
The PMO noted the other arteries and heart were found with no discernible abnormality, therefore, the conditions had not dispersed through the cardiovascular system. The PMO also reported that it could not be determined with certainty if the pilot experienced abnormal heart rhythm unless the heart was being actively monitored. Queensland Health reported that the ‘consequences of high blood pressure as a clinical issue were not noted in the autopsy report. In particular, there was no evidence of a stroke and no indication of a heart attack’.
The Cloncurry DAME reported the dosage of Irbesartan was moderate and that it ‘would have been unlikely to cause any symptoms of hypotension causing dizziness or disorientation’. Queensland Health and the PMO reported that missing a single dose of Irbesartan would not be likely to cause any issues clinically.
Wreckage and impact information
The wreckage examination included an initial on-site inspection, followed by a review of the accident site images. The photographic review resulted in a second accident site visit to excavate the wreckage and retrieve a component of interest, which was the bellcrank from the cyclic control assembly.
Initial on-site examination
The helicopter wreckage was located amongst termite mounds, in a sparsely treed area. The main wreckage had been subject to a significant post-impact fire, which had reduced the cabin area to ash, molten aluminium, and fibreglass mat. The airframe was oriented south-east on a heading of about 140°, which was in the opposite direction to the helicopter’s recorded flight path. Small pieces of debris were scattered around the wreckage in a radius of about 20 m in most directions. The windscreen perspex was unburnt, shattered into small pieces and contained in an area of about 2 m2 just forward of the cabin area. All the major components were identified within the debris field (Figure 5).
Figure 5: Main wreckage
Source: ATSB
The airframe impacted the ground on the front left. Compression damage to the forward vertical firewall of the helicopter indicated that it impacted with a high rate of descent.
The helicopter’s main rotor disc had severed the tailcone and tail rotor driveshaft, leaving paint transfer on the driveshaft and tailcone. There were multiple strikes to tail components, which included the tail rotor hub and vertical stabiliser, generating a pattern of tail strike debris. The pattern was noted to be in a semi-circular arc on the right side of the main wreckage with respect to the direction of the GPS track. This was consistent with the helicopter tracking away from the airport and towards the powerlines at the time of the tailcone strike.
The main rotor blades exhibited rearward and upward bending, and there was no evidence of rotor blade ground strike marks or damage to the surrounding termite mounds. This was consistent with a significant loss of main rotor energy before ground impact, which was a near vertical impact. The teeter stops were destroyed by fire, but one teeter stop bracket was damaged and the associated main rotor blade spindle tusk[24] had a slight bend. This indicated the teeter stop bracket was struck by its respective main rotor blade spindle.
There was no evidence of any significant tension on the tail rotor driveshaft aft flexible coupling and little evidence of bending on the severed aft section of driveshaft (Figure 6). This indicated it was likely a power-on, high energy, main rotor strike to the tail.[25] The section of driveshaft forward of the severed section exhibited elongation and a bending overload, which indicated it was rotating during the break-up sequence. Therefore, the damage to the driveshaft was consistent with the main rotor disc striking the tail under normal engine power and rotor speed conditions.
Figure 6: Severed tail rotor driveshaft
Source: ATSB
The forward flexible coupling of the driveshaft exhibited significant tension. According to RHC, flexing of the main rotor mounts will change the angle of the input yoke of the main gearbox, which will cause the yokes at the flexible couplings to move apart. The tension on the forward flexible coupling, damage to the teeter bracket, and angle of the tailcone strike were consistent with a large rearward tilt of the main rotor disc in-flight past its normal limits.
On completion of the ATSB’s initial onsite inspection, the operator and next-of-kin buried the wreckage adjacent to the impact site.
Excavation
During the photographic review of the wreckage after the initial on-site inspection, the ATSB noted an anomaly with a flight control bellcrank (part number A958-1) in the cyclic control assembly. The fastener,[26] which attached the horizontal push-pull tube (part number A121-1) to the bellcrank, was missing. The remaining bellcrank fasteners were all attached. The missing fastener was part of the longitudinal cyclic control, which controls the fore-aft tilt of the main rotor disc (Figure 7). The RHC R22 Illustrated Parts Catalog (IPC) showed that the flight controls should be secured at the bellcrank with a National Aerospace Standard (NAS) 6604-15 bolt and D210-4 self-locking nut.[27]
Figure 7: Longitudinal cyclic control
Source: Robinson Helicopter Company, modified by the ATSB
The ATSB returned to Cloncurry in February 2018, and with the assistance of the pilot’s next‑of‑kin, the next of kin’s support persons, and the Cloncurry State Emergency Service personnel, excavated the majority of the buried wreckage and retrieved the bellcrank minus the missing fastener hardware. In addition to the bellcrank, the ATSB retrieved several pieces of resolidified metal to examine for the presence of hardware (bolt, standard washer, lockwasher, rod-end and self-locking nut).
In May 2018, the next-of-kin, who had continued excavating the remainder of the wreckage, sent a bolt with the same part number as the missing bolt (NAS6604-15) to the ATSB.[28] Following receipt of the bolt, the ATSB, in consultation with RHC and the next-of-kin, verified that all the remaining NAS6604-15 bolts were still attached to their respective assemblies.[29] This included the bolts not identified in the IPC as they are not normally accessible. As such, the bolt recovered from the excavated wreckage was considered very likely to be from the missing fastener. Figure 8 depicts the bellcrank and bolt.
Figure 8: Bellcrank with missing fastener (left) and bolt (right)
Source: ATSB (left) and next-of-kin (right)
Effect of loss of longitudinal cyclic control
The ATSB enquired with RHC about the expected response of the main rotor system to a disconnection of longitudinal cyclic control. They advised that:
During straight and level flight the A121-1 push-pull tube is under compression load. This pushes the cyclic aft [pilot’s cyclic stick]. A bungie cord is attached to the forward end of the tube (pulling aft, below the cyclic pivot point) to counteract the forces and neutralizes the loads felt by the pilot. The loads increase with airspeed.
With reference to Figure 7, a compression load on the A121-1 push-pull tube is consistent with a force tilting the main rotor disc aft and pushing downwards on the aft vertical push-pull tube. In forward flight, the advancing main rotor blade is at a higher airspeed than the retreating blade, which increases the lift on the advancing blade relative to the retreating blade. The reaction to this dissymmetry of lift is that the advancing blade flaps up and the retreating blade flaps down, which the pilot corrects with forward cyclic input as airspeed increases (Wagtendonk, 2011). Therefore, a disconnection of the longitudinal cyclic control in forward flight will result in the rotor disc tilting aft, potentially striking the tailcone.
Tests and research
Following identification that the rear fastener for the cyclic assembly horizontal push-pull tube was missing from the bellcrank, a number of items were recovered from the accident site and retained for further examination at the ATSB’s technical facilities in Canberra. The items included:
the bellcrank – part number A958-1
a bolt – part number NAS6604-15 (recovered by the next-of-kin on 16 May 2018)
metallic debris (that had melted during the post-accident fire then resolidified on cooling)
a number of loose nuts and washers
a jackshaft – part number A337-1 – including attachment nuts and bolts
the forward support assembly – part number A014-6.
A summary of the main findings from the examination is provided here, for full details of the examination refer to Appendix A – Materials examination report. The scope of the examination was to analyse the bellcrank and related components to determine how the fastener came to be missing. In addition, the metallic debris recovered from site was examined to determine if any additional fastener parts were entrapped within the solidified mass.
Bellcrank and related components
The bellcrank and torque tube yoke assembly had been subject to significant mechanical damage such that the rod ends had fractured in overstress and the left side of the yoke assembly and bellcrank plate had significantly distorted. While the distortion of the plates was similar where the fasteners remained in position, the plates had been pushed together where the fastener was missing (Figure 9). The yoke assembly also exhibited heat damage in this area, with the left side moulding around the bellcrank plate. The combination of mechanical and heat damage meant that an exemplar bolt could not be reinserted through the bellcrank.
Figure 9: Bellcrank showing deformation observed on the torque tube yoke assembly and bellcrank plates
Source: ATSB
The bolt holes where the fastener was missing did not exhibit gross deformation or elongation of the holes to indicate that the fastener assembly had been forcibly removed during the accident sequence. Yellow colouration was observed around the other bolt holes where the fasteners had remained in position. While some yellow colouration was observed around the bolt hole of the missing fastener, it was much less than for the other holes, and none was observed around the internal surfaces of the hole (Figure 10).
Figure 10: Bellcrank internal surfaces with yellow colouration
Source: ATSB
Robinson reported that the yellow residue surrounding the fasteners was from the cadmium plating on the bolts, washers and screws.[30] The remnants of cadmium plating from the fastener assembly components had melted and subsequently oxidised during the post-accident fire. The residue surrounding the bolt hole for the missing fastener indicated the missing bolt was previously torqued, resulting in a transfer of cadmium from the washer to the bellcrank. However, as there was no outward flow, or streaking, as per the remaining fasteners, RHC considered it ‘highly unlikely that the missing bolt was present during the fire’.
The combination of the above observations indicated that the missing bolt was not fitted to the bellcrank at the time of the impact with terrain and post-impact fire.
The remaining two bolts installed on the bellcrank were identified as NAS6604-15 bolts and the nuts were consistent with the MS21042L4/NAS1291 nut-type with manufacturer markings consistent with Ronson Manufacturing Inc.
Metallic debris
The metallic debris was dissolved, and a number of fasteners and other components were recovered. However, examination of the pieces did not identify any parts from the missing fastener.
Recovered bolt
The solitary bolt found on 16 May 2018 by the next-of-kin was identified as a NAS6604-15 bolt. The bolt had the same manufacturer identification (‘LFC’) as the other two bolts fitted to the bellcrank, but exhibited greater fire damage (Figure 11).
Figure 11: Comparison between the bolts removed from the bellcrank (left and centre) and the fire damaged bolt (right) subsequently recovered from the accident site
Note: The recovered bolt is shown after it had undergone ultrasonic chemical cleaning.
Source: ATSB
The recovered bolt was thermally damaged from the post-accident fire, but was otherwise in good condition with no evidence of distortion along its length or to the threads. A small groove was identified on the thread flank, which was likely from contact with a self-locking nut during installation (Figure 12).
Figure 12: Magnified image of the bolt found 16 May 2018 showing thread groove
Source: ATSB
Jackshaft
Examination of the jackshaft assembly recovered from the wreckage found that three of the four self-locking nuts had the same manufacturer markings as the nuts fitted to the bellcrank. Fire damage precluded identification of the markings on the fourth nut.
Semi-quantitative chemical analysis of the nuts was conducted using a scanning electron microscope equipped with an Oxford energy dispersive x-ray spectrometer. The analysis confirmed that all four nuts were consistent with a carbon/alloy steel. While the spectrometer cannot determine the exact amount of alloying additions, the spectrographs for the four nuts were inconsistent with the CRES (corrosion resistant – stainless steel) D210-4 nuts specified to be used by RHC. Specifically, the nickel, chromium and molybdenum additions, where detected, were not of sufficient quantities to designate the nuts as stainless steel (see Previous safety issues - self-locking nuts).
Maintenance of the cyclic control assembly
During their interviews with the ATSB in 2018, the CAM staff[31] could not recall the specific details of the work they individually performed on the cyclic control system of VH‑HGU during the 2,200‑hour overhaul. However, they were able to provide a description of the normal process they followed for the removal, inspection, installation and inspection of the cyclic control assembly. The physical process, as described by CAM staff, was consistent with the process published and described by RHC.
Removal
The removal process involved the vertical push-pull tubes being unscrewed from the bellcrank and yoke rod-ends, then the remaining components from the cyclic stick through to the bellcrank would be removed from the airframe as a single unit. After removal from the airframe, the length between the bolt holes for the horizontal push-pull tube would be measured for use during reassembly. There was no record of this measurement in the work-pack for VH-HGU, however, the maintenance manual provided a standard length that could be used for the installation.
The horizontal push-pull tube forward fastener would then be disconnected from the cyclic stick and the horizontal push-pull tube unscrewed from the bellcrank rod-end. Therefore, the bellcrank fasteners were not required to be disassembled during this part of the process. The cyclic stick is separated from the torque tube, but the bellcrank can remain attached to the torque tube with the fasteners and rod-ends fitted, as neither of these components required non-destructive testing.
Inspection
The bellcrank is inspected for cracks and corrosion, and the rod-ends are tested for axial and radial play (Figure 13). According to RHC, the play in the rod-ends can be checked without removal from their respective fastener. The CAM staff reported that the rod-ends would initially be checked for play without their removal, and then only removed for measurement with a dial test indicator if there was doubt. The chief engineer reported that the rod-end would be replaced if it had reached half the permitted tolerance as the wear will accelerate and it was preferable to replace them at the 2,200-hour overhaul, rather than at a 100-hour inspection.
Figure 13: Rod-end and spherical bearing play limits
Source: Robinson Helicopter Company, annotated by the ATSB
There was no record in the work-pack to indicate that any of the bellcrank rod-ends were replaced or disturbed for inspection. However, other than what the maintenance manual specified for the overhaul, disturbances of the flight controls were not recorded in the work-pack unless a part was replaced. Several rod-ends from other assemblies were replaced during the overhaul, and they were accounted for by a cross-check between the ‘parts list’ and ‘aircraft worksheet’ sections of the work-pack.
Installation
After removal and disassembly, the push-pull tubes and cyclic stick would then be stripped of their paint and sent for non-destructive testing. All parts for VH-HGU were found serviceable from non‑destructive testing, and on return, they were painted and re-assembled. One of the apprentices reported the cyclic assembly could be removed and installed by an individual, but it was more common to use two persons, ‘depending on what was going on’. In August 2017, the chief engineer could not recall who refitted the parts returned from non‑destructive testing. The installation was certified as having been performed by the AME (aircraft maintenance engineer). However, in February 2018, the AME could not remember anything about this work.
The AME reported that the chief engineer would normally inspect the cyclic when re‑assembled, and again when it was installed. After installation, the chief engineer would assist the AME with the rigging process and then perform an ‘inspection and make a list and get them to fix it… and then get [head engineer] in to check’. The fourth year apprentice was reportedly involved in the disassembly, reassembly and rigging, but was unsure about the first year apprentice’s involvement. The first year apprentice was reportedly involved in the disassembly, but was at trade school 1–13 July 2017, and missed some of the reassembly.
According to RHC, if the cyclic assembly is installed and the horizontal push-pull tube has the incorrect length between bolt holes, then it is easier to remove the aft rod-end (bellcrank fastener) to make the length adjustment. However, this is most likely to be discovered during the rigging process and compensated for by adjusting the vertical push-pull tube lengths or pitch links, unless it is excessively far from the specified dimension. The chief engineer reported that for the rigging adjustments they ‘generally do it on the upper push-pull tubes—wind them all the way in and then adjust at the top—sometimes the lower push-pull tube, but don’t recall having any trouble with the accident helicopter’.
The head engineer reported that the cyclic assembly fasteners are torqued and torque striped[32] before the assembly is installed, which is when the independent inspections for correct assembly would be performed. After installation, the head engineer would perform an independent inspection for correct fitment and clearances. The head engineer would then provide a list of discrepancies to the chief engineer, and then re‑inspect after any adjustments had been made. As the work-pack was not used to record discrepancies and adjustments, it could not be determined if any discrepancies were found or if any adjustments were performed.
100-hour inspection
After the helicopter had been assembled and the flight controls rigged, the next step in the overhaul procedure was for a 100-hour inspection to be performed. For VH-HGU, this inspection was certified by the AME and chief engineer using a CAM form, which was a one-page abbreviated checklist. The CAM checklist condensed the RHC R22 maintenance manual certification requirements from 226 items to 19 items. Consequently, each item in the CAM checklist accounted for between 1-30 separate inspection items. However, the CAM checklist specifically stated that the 100-hour inspection checklist was to be used in conjunction with RHC maintenance manual.
Figure 14 shows a comparison of the CAM checklist item (left) with the RHC R22 maintenance manual (right) for the removal of the horizontal cover cyclic box cover, belly panel and vertical panel. The depiction below of the maintenance manual is one of three pages under the heading 4 task certifications. Inspection of the cyclic push-pull tubes, bellcrank and fasteners were items 19, 20 and 26. These items were covered as item 4 in the CAM abbreviated checklist.
Figure 14: Comparison of the CAM 100-hour inspection checklist (left) and the R22 maintenance manual (right)
Source: Cloncurry Air Maintenance (left) and Robinson Helicopter Company (right), annotated by the ATSB
Certification for the work
Item 18 of the CAM checklist was for the installation and closure of all access panels on completion of the 100-hour inspection. At interview in August 2017, the chief engineer reported that the certification for independent inspections was after the rigging, but before the panels were installed and the fuel tanks calibrated. However, the work-pack suggested that the fuel calibration was recorded before certification for independent inspections, which was the last entry in the ‘aircraft work-sheets’ section of the work-pack.
At the completion of the 100-hour inspection, the helicopter was to undergo a ground run, track and balance of the main rotors, autorotation RPM check and flight check. The work-pack showed that the AME certified for the ground check and run-up, a fanwheel and tail rotor balance, the track and balance of the main rotor and autorotation RPM check.
Of note, the AME was not qualified to ground run the helicopter, and the pilot for the track and balance flights was reportedly following the chief engineer’s instructions for the flights, not the AME. The pilot and chief engineer both reported that several flights were required for the track and balance of the main rotor, with adjustments made between the flights.
No entries in the work-pack were found for any track and balance adjustments, or for the check flight, which was required to follow the track and balance, and autorotation RPM check flights. The chief engineer reported that they were not using the maintenance manual checklists for these steps of the overhaul procedure. Instead, loose paper was used, which was not retained in the work-pack. Therefore, it was unknown what adjustments were made to the helicopter.
The work-pack showed that the AME certified for all the tasks in the aircraft work-sheets on 31 July 2017 and the chief engineer certified for the supervision on the same date.[33] Although there was no date recorded for the certification for independent inspections, it was considered likely that it was on the same date as this was the last entry in the work-sheets. Similarly, the 100‑hour inspection certification was also not dated, but considered likely to have also occurred on the same date.
The ATSB noted that the single date certification at the end of the overhaul was not in accordance with the CAM Maintenance Procedures Manual (MPM). The MPM Part 6.10: Scrutiny of Work and Certification, required progressive certification for each ‘item as it is completed on the work package’.
Organisational and management information
Organisational structure
Cloncurry Mustering Company’s primary operations were cattle mustering and other airwork from their main base at Cloncurry Airport. The majority of maintenance conducted on their fleet of 23 R22 and four R44 helicopter’s was performed by CAM, which was an associated company. In addition to this, CAM also performed work on external helicopters for other operators.
The facilities in Cloncurry were used by both CAM and CMC, and they had the same managing director (MD) and shareholders. The shareholders included the MD, chief engineer and several of the CMC senior pilots, including the accident pilot. The chief engineer for CAM also held the position of maintenance coordinator [34] for CMC.
One of the key positions in an operator’s organisational structure is the Head of Aircraft Airworthiness and Maintenance Control (HAAMC). The position of HAAMC provides an interface with maintenance organisations for the planning and preparation of maintenance activities, and an independent check of the completion of those activities when an aircraft is returned to service.
The MD was issued with the CMC HAAMC approval by CASA in June 2005. According to the letter of approval, the HAAMC ‘has the responsibility for all airworthiness matters relating to the aircraft operated under the AOC [Air Operator Certificate]’. Within the CMC operations manual, the responsibilities of the HAAMC were delegated to the maintenance coordinator (chief engineer). The ATSB considered this a pragmatic decision, as the chief engineer was the individual most suitably qualified and experienced for the role and responsibilities. However, it resulted in the two key positions of interface between CAM and CMC for maintenance and airworthiness matters being held by the same person.
Cloncurry Air Maintenance
Maintenance approval
Cloncurry Air Maintenance had a Certificate of Approval for the maintenance of piston-engine helicopters with a maximum take-off weight not exceeding 3,175 kg. Their approval included the maintenance of airframe, engines, engine components, and electrical components fitted to, or eligible to be fitted to, R22 and R44 helicopters. In accordance with Civil Aviation Regulation1988, Section 30, CAM had a documented set of quality control procedures, published as their Maintenance Procedures Manual (MPM).
Workforce
In 2013, the CAM workforce comprised of four licenced aircraft maintenance engineers (LAMEs) and two apprentices. By the time of the accident, in August 2017, the workforce structure had changed to two LAMEs (the chief engineer and head engineer), one AME and three apprentices. All of these employees had been trained by CAM from the time of their apprenticeships.
The division of work for CAM required the chief engineer to manage the CMC helicopters, while the head engineer managed the external helicopters. The two LAMEs would support each other for independent inspections, with the chief engineer certifying for the independent inspections of external helicopters, and the head engineer certifying for the independent inspections of CMC helicopters. The AME and two apprentices were allocated to the CMC helicopters and the third apprentice allocated to support the head engineer working on the external helicopters. The two apprentices working on the CMC helicopters were a first year and fourth year apprentice. The first year apprentice was required to attend trade school and therefore not always present.
The chief engineer reported that it was difficult to recruit a LAME workforce into Cloncurry, due to its remote locality, and that alternative apprenticeship schemes might be perceived as less demanding with more attractive remuneration. The MD believed that the LAME recruitment problem was not limited to their business and that it was a wider problem, which also affected businesses on the east coast.
Workload
The cattle mustering season from April to September required an increase in the maintenance workload through the middle of the year to keep the CMC helicopters operating. The CAM hangar space facility was divided between a main area, where several helicopters could be parked for 100-hour inspections, and two separate 2,200-hour overhaul rooms dedicated for one CMC helicopter and one external helicopter.
At interview, none of the maintenance staff could recall any specific details associated with the disassembly and reassembly of the cyclic control assembly during the overhaul on VH-HGU. All staff reported it was a busy period and that the overhaul was routinely interrupted for 100-hour inspections. In the month of July 2017, 21 100-hour inspections were commenced on CMC helicopters and 20 were completed, in addition to progressing the overhaul of VH-HGU to completion on 31 July (plus one external helicopter in overhaul).
Robinson reported that a 100-hour inspection should take about 24 labour-hours to complete. Therefore, to complete 20 inspections in the month of July would require about 480 labour‑hours. This would have required about three qualified staff (LAME/AME) working full time on the 100 hour-inspections for CMC helicopters, plus additional staff to progress the overhaul of VH-HGU. A calendar break-down of the 100-hour inspections and 2,200-hour overhauls for the CMC helicopters over the months of July and August is provided at Appendix B – Maintenance workload.
Quality assurance
Internal audits
Part 8 of the CAM MPM described the purpose of their internal audit program was:
…to ensure that the effectiveness and performance of the Company and the procedures documented in the Maintenance Procedures Manual are continually being measured and assessed.
As they did not have a quality manager position, and none was required, CAM contracted an external auditor to perform their internal audits. The ATSB reviewed the two internal audit reports produced for CAM in 2015 and 2016, and noted that each had been performed by a different auditor.
The December 2015 audit included a review of three work-packs and ‘nil findings’ were recorded against them. The November 2016 audit included a review of one work-pack and ‘nil defects’ were recorded. Both audit reports concluded with ‘nil non-conformances’, ‘nil requests for corrective action’ and ‘nil suggestions for system improvement’.
The work-pack sampled for the 2016 audit was for an R22 100-hour inspection. The ATSB reviewed this and noted the CAM 100-hour inspection abbreviated checklist was used and that all work was certified on the same day as performed by one LAME. In this instance, a single certification was provided for the ground check, run up and all 19 items on the abbreviated checklist.
Civil Aviation Safety Authority oversight
The CASA Cairns office was responsible for oversight of CAM. In the period from June 2013 to January 2018, 22 entries were made in the CASA database for their oversight of CAM. They included nine references to ‘nil’ or ‘no major issues’ and five references to CAM as a ‘compliant organisation’
On 13 May 2015, an audit was conducted on CAM by one CASA airworthiness inspector for one day. On 22 June 2015, the auditor entered into the database for CAM ‘recent audit carried out on Western Planes [plains] Sweep – compliant organisation’. The May 2015 visit was their last audit of CAM prior to the accident on 2 August 2017.
2015 audit
In the May 2015 CASA audit report summary, the auditor reported that CAM ‘was assessed against the regulatory requirements within the system listed below (scope)’. The elements included:
maintenance activity
data and documents
tooling and equipment
stores and distribution.
The auditor assessed CAM compliance against the MPM and did not identify any breaches of the regulations. Two observations were issued as opportunities for improvement.[35]
The audit report stated that:
Control of Maintenance Activity was assessed compliant when audited against Chapter 6 of the MPM. The Chief Engineer is conducting all duties as detailed in the MPM and controls the company workpacks and maintenance activities.
Sampling was conducted on three workpacks…with no issues identified.
The ATSB obtained a copy of the 2,200-hour overhaul work-pack sampled by the auditor. This was for an R22 helicopter, for which the overhaul was completed in 2015. The work-pack omitted several steps of the overhaul procedure, specifically, there were no entries for the 100-hour inspection, ground run, run up and check flight. While the track and balance was recorded and certified in the work-pack, there were no records for any adjustments. The entire work-pack was certified with a single date, which indicated progressive certification was not employed as required by the CAM MPM.
The auditor’s notes did not reveal any further information about the CAM audit than what was recorded in the report. However, of note, the auditor did not retain copies of the work-packs sampled. Instead, the auditor’s notes included photographs of the front pages of the work-packs. The report was certified by the auditor and approving officer on 25 May 2017.
2018 audit
After the accident, on 10–11 April 2018, CASA conducted an unscheduled Level 1 surveillance audit of CAM. The team comprised one airworthiness inspector and one engineering officer. During the course of the CAM audit, several findings were identified as airworthiness matters. This resulted in the expansion of the scope of the audit to include CMC.
The expansion of the scope resulted in CASA issuing two reports, one for CAM (the maintenance organisation) and one for CMC (the operator). The audit sampled several work-packs, which included the 2,200-hour work-pack for the R22 helicopter that started overhaul on 1 August 2017. The auditors made similar findings to what the ATSB noted for the work-pack for VH-HGU and the CASA 2015 audit of CAM. They included the following issues:
Use of abbreviated checklists: The certification points in the company abbreviated 100-hour inspections checklists did not reflect the content of the inspection items listed under them in accordance with the RHC R22 maintenance manual. The use of abbreviated checklists relied on the maintenance staff continually referring to the maintenance manual to identify all the inspection items under each heading. The inspectors recommended CAM review the suitability of using abbreviated inspection checklists.
Independent inspections: The 2,200-hour work-packs sampled found one independent inspection performed at the end of the overhaul. Given the scope of the overhaul and level of disassembly, reassembly and adjustments required, the auditors recommended that independent inspections are certified progressively and noted that additional inspections would be required for each adjustment of flight control components during the tracking and balancing procedure.
Flight without a maintenance release: The chief engineer confirmed that it was their standard procedure to complete the flying tasks within the 2,200-hour overhaul before issuing a new maintenance release. Therefore, the helicopters were being flown without a valid maintenance release.
Maintenance coordinator responsibilities: A number of helicopters were released to service without complying with their approved maintenance program. The CMC operations manual required the maintenance coordinator check all maintenance was completed before an aircraft was returned to service.
Previous occurrences involving fasteners
CASA R44 service defect report
On 17 May 2018, another operator’s Robinson R44 helicopter completed a 2,200-hour overhaul, which included the replacement of the flight control hydraulic servo assemblies. The overhaul was certified by a LAME and with an accompanying independent inspection certification. On 26 February 2019, the operator submitted a service defect report to CASA following a pilot report of ‘deterioration of flight control inputs along with banging sound coming through airframe’.
On inspection, the bolts used to secure the hydraulic servos to the support bracket were found to have insufficient torque. The MS21042L-series nuts had not been replaced with D210-series nuts (see Re-use of self-locking nuts below), and no Palnuts®[36] were fitted as secondary locking devices in accordance with the instructions for continued airworthiness. The inadequate torque allowed movement of the servos, which resulted in elongation of the NAS6600-series bolts and the bracket bolt holes. Of note, despite the insufficient torque and elongation of the bolts, the MS21042L-series self-locking nuts fitted to the bolts had not failed or undone.
United States National Transportation Safety Board (NTSB/AAR-13/01)
On 7 December 2011, a Eurocopter AS350-B2 helicopter, operating as a ‘Twilight tour’ sightseeing trip, crashed in mountainous terrain about 14 miles east of Las Vegas, Nevada. The pilot and four passengers were fatally injured, and the helicopter destroyed. The United States National Transportation Safety Board (NTSB) found that the accident was a result of an in-flight disconnect of the flight controls, specifically, the separation of the servo control input rod from the main rotor fore-aft servo, which rendered the helicopter uncontrollable. The bolt, washer, self‑locking nut, and split pin that normally secured the input rod to the fore-aft servo were not found. It was concluded that the hardware had been improperly secured during maintenance the day before the accident
The NTSB found there was inadequate maintenance of the helicopter, including (1) the improper reuse of a degraded self-locking nut, (2) the improper or lack of installation of a split pin, and (3) inadequate post-maintenance inspections. They reported the contributing factors included personnel fatigue for the mechanic and inspector, and the lack of clearly delineated maintenance task and inspection steps.
On 12 October 2011, the pilot of a Robinson R22 helicopter, registered VH-JNP, was performing aerial work near Saxby Downs, Queensland, when a rattling noise from behind the cabin was heard by the pilot, who also noted the clutch light had illuminated. The pilot opened the clutch actuator circuit breaker and, at the same time, noted a burning rubber smell. The pilot made an immediate precautionary landing and shut down the helicopter.
The problems with the helicopter’s drive system were traced to the clutch assembly where a group of MS21042L-4 self-locking nuts on the drive belt upper sheave had cracked and fractured. This premature nut failure had stemmed from the likely embrittling effect of residual hydrogen generated during the cadmium electroplating process applied during manufacture. All of the affected self-locking nuts were identified as Airfasco Industries Fastener Group (affected batches identified as 12 June 2009, 23 October 2009 and 19 October 2010). They were fitted in April 2011, at the last 2,200-hour overhaul. Since that time, the helicopter had operated for a further 408 hours and was subject to four 100-hour inspections during that period.
On 4 February 2011, a Robinson Helicopter Company R44 Astro helicopter, registered VH‑HFH, commenced circuit operations at Cessnock Airport, New South Wales. Following a landing as part of a simulated failure of the hydraulic boost system for the helicopter’s flight controls, the instructor elected to reposition the helicopter to the apron. As the helicopter became airborne, it became uncontrollable and collided with the runway and caught fire. The pilot survived, but the instructor and a passenger were fatally injured.
The ATSB found that a fastener had detached from a hydraulic-boost servo, rendering the helicopter uncontrollable. The hydraulic-boost servo was repaired and functionally tested by the manufacturer in February 2009. The servo spent the majority of its time as a spare in storage before it was installed on VH-HFH in October 2010 during the last 100-hour inspection. The helicopter accrued 93.6 hours in-service prior to the accident. The bolt was recovered and noted that there was no distortion, and its threads and shank were visually undamaged. However, the remaining fastener parts were not recovered.
Previous safety issues – self-locking nuts
Hydrogen embrittlement
In the final investigation report of AO-2011-016, as mentioned above, the ATSB examined three cracked self-locking nuts from other R22 helicopters, of the same specification as that fitted to the detached fastener on the accident helicopter. These nuts were found to have cracked due to hydrogen embrittlement. Specifically, the report stated that:
When high-strength steel, which has been exposed to hydrogen is sufficiently stressed, it can fail prematurely in a sudden, brittle manner. In the case of the examined self-locking nuts, the source of hydrogen was likely to have been from the cadmium plating process that was specified during manufacture for corrosion resistance. Under conditions of sustained stress, such as that associated with an assembled fastener, plus any residual tensile stresses from manufacturing, the presence of hydrogen can result in brittle cracking, typically less than 1 week from the time of application of the sustained stress.
In response to the identification of the hydrogen-embrittled self-locking nuts, the ATSB raised the following safety issue (AO-2011-016-SI-01 – Self-locking nut failure) on 30 April 2012, affecting owners and operators of RHC helicopters:
A number of self-locking nuts from other aircraft, of the same specification as that used to secure safety-critical fasteners in VH-HFH, were identified to have cracked due to hydrogen embrittlement.
During the course of the investigation the ATSB was provided with three self-locking nuts from other aircraft that had cracked in service. Detailed examination of those nuts identified that they had failed due to hydrogen embrittlement. In response to that finding, the ATSB notified the helicopter manufacturer, the Civil Aviation Safety Authority (CASA) and the United States National Transportation Safety Board and Federal Aviation Administration.
At the time of publishing that investigation report and safety issue, RHC had reported the following proactive safety action in response to the safety issue:
In response to the identification of hydrogen-embrittled self-locking nuts during this investigation, the helicopter manufacturer issued service letters (SL-58, SL-38 and SL-01),[37] which detailed the hydrogen-embrittlement risk, including the expected failure characteristics.
The Civil Aviation Safety Authority also reported the following proactive safety action at the time of publishing:
In response to the identification of hydrogen-embrittled self-locking nuts, CASA issued Airworthiness Bulletin 14-002, on 12 October 2011, alerting aircraft owners, operators and maintenance personnel to the possibility of in-situ failures of MS21042 and NAS1291-series self-locking nuts. The bulletin provided background information on previous occurrences and the mechanism and hazards associated with hydrogen embrittlement, and recommended that:
Pilots and maintenance personnel closely monitor the occurrence of hydrogen-induced delayed cracking in high-strength steel standard aircraft hardware, such as nuts via close inspection following installation and thereafter at Daily / Preflight and periodic inspections.
Before simply replacing cracked/failed nuts with new items, consider contacting the manufacturer for advice regarding replacement of associated fasteners which may have suffered over-loading as a result of the failure of one of more nuts.
Report all MS21042 and NAS1291-series nut failures to CASA via the SDR [Service Difficulty Reporting] system.
Re-use of self-locking nuts
As explained above, cracking from hydrogen embrittlement of nuts fitted to Robinson helicopters has been previously identified.[38] In October 2014, RHC published service letters for the R22 (SL‑64), R44 (SL-50) and R66 (SL-09) helicopters on the subject of D210 Corrosion-Resistant (CRES) Nuts.[39] The service letters stated that, whenever maintenance that involves the disassembly and reassembly of a critical fastener is performed, the MS21042L or NAS1291-series nut should be replaced with a D210-series nut. The R22 maintenance manual was amended in October 2014 to incorporate what was stated in SL-64. For specific instances of cracked nuts, RHC have published service bulletins for their replacement within a compliance period.[40]
The R22-series maintenance manual included the following information under section 1.300 Fastener Torque Requirements:
D. Critical Fastener: A critical fastener is one which, if removed or lost, would jeopardize safe operation of the helicopter. This includes joints in the primary flight control system, and non-fail-safe structural joints in the airframe, landing gear, and drive system.
CAUTION: D210-series nuts, which supersede MS21042L-series and NAS1291-series nuts, are required on critical fasteners.
In the course of interviewing maintenance personnel employed by CAM, the ATSB noted a low‑level of awareness of the need to replace self-locking nuts with the D210-series nuts when critical fasteners were reassembled. However, the staff were aware of the limitation on the re-use of them, specifically, that they could not be reused if they had lost their friction torque. It is a standard practice within sectors of the aviation industry to re-use self-locking nuts provided the nut cannot be turned onto the bolt thread by hand and the published torque value for the fastener is achieved.[41]
During the course of the investigation, the ATSB spoke with another maintenance organisation, who reported that they employ the same practice of re-using self-locking nuts, and RHC confirmed that the described practice was considered acceptable. The United States NTSB reported on this practice as accepted by the manufacturers of light helicopters in their accident report AAR‑13/01.[42] They noted that guidance on the re-use of self-locking nuts was provided by Eurocopter (now Airbus Helicopters), Sikorsky, Bell and the United States Federal Aviation Administration.
In December 2018, the ATSB received the accident helicopter’s jackshaft, which had the fasteners attached. The jackshaft was one of a number of parts within the flight control system that was disassembled and sent for non-destructive testing during the 2,200-hour overhaul. The bellcrank was not subject to non-destructive inspection and therefore not required to be disassembled. In late January 2019, the ATSB completed semi-quantitative chemical analysis of the nuts fitted to the jackshaft and found they were consistent with a carbon/alloy steel, and therefore not consistent with D210-series stainless steel corrosion-resistant nuts. The nuts fitted to the jackshaft had similar markings to the nuts fitted to the bellcrank, which were consistent with MS21042L/NAS1291-series nuts.
At the time of the reassembly of the accident helicopter, the current R22 Illustrated Parts Catalog listed the part number D210-4 for the nuts fitted to the jackshaft, and RHC confirmed there were no alternate part numbers to the D210-series nuts.
In consideration of the evidence, the ATSB concluded that the industry practice of re-use of self‑locking nuts on Robinson helicopters may result in the omission to install D210-series nuts when critical fasteners are reassembled. Therefore, as part of this investigation, the ATSB issued a safety advisory notice (AO-2017-078-SAN-001) on 28 March 2019.
Memory-related errors
In the 2008 ATSB research report An Overview of Human Factors in Aviation Maintenance (AR-2008-055), it was noted that ‘poor maintenance procedures can lead to a range of errors including memory lapses, technical misunderstandings, and rule violations’.
Certification for a task after an extended period of time, in which multiple similar tasks were performed, can result in the misattribution of the source of memory at the time of certification. Misattribution of the source of a memory occurs when an individual recalls an item or fact from a past experience, but attributes it to an incorrect source of experience (Schacter, 1999). In the case of aviation maintenance, certifying for an inspection on aircraft A, when in fact it was performed on aircraft B, would be an example of possible source misattribution.
Closely related to source misattribution is the phenomena of suggestibility. The difference is that suggestibility includes an overt suggestion (Schacter, 1999). Presenting maintenance staff with a work-pack of recorded tasks for certification may introduce the suggestion of work completed, particularly if this is associated with the knowledge of a serviceable assessment from an operational check. This could result in staff certifying for tasks because they are listed on the work-pack for certification, rather than because they remember performing them.
Source misattribution and suggestibility are examples of retrospective memory errors at the time a certification is made. However, maintenance documentation is also important for prospective memory, which is remembering to complete a task in the future. According to Dismukes and Nowinski (2007), prospective memory is distinguished by three features: (1) an intention to perform an action at some later time when circumstances permit; (2) a delay between forming and executing the intention, typically filled with activities not directly related to the deferred action; and (3) the absence of an explicit prompt indicating that it is time to retrieve the intention from memory.
If an inspection of a system identified a requirement for re-work, and the re-work was completed at a time that the inspector was not available to re-inspect the work, then an omission to re-inspect would be an example of a possible prospective memory error. In this case, recording the disturbance (re-work) in the work-pack would provide a prompt to all relevant staff members that an independent inspection is required before the aircraft can be released from maintenance.
On the morning of 2 August 2017, the pilot of a Robinson R22 Betta II helicopter, registered VH‑HGU and operated by Cloncurry Mustering Company (CMC), departed Cloncurry Airport, Queensland on ferry flight in preparation for aerial mustering operations at various stations. About 3 minutes after take-off, the pilot experienced a loss of control and the helicopter broke-up in-flight. The helicopter collided with terrain about 7 km north-north-west of Cloncurry. The pilot, who was the only occupant, was fatally injured and the helicopter was destroyed. The accident flight was the first commercial flight of the helicopter after completing its second 2,200-hour overhaul.
While the pilot’s post-mortem examination identified coronary atherosclerosis, there was no evidence of a heart attack or stroke. Although it was noted that any conclusions could not be based on the examination alone. Despite this, the witnesses who encountered the pilot on the morning of the accident reported the pilot’s demeanour as normal. Further, a review of the GPS data did not find any indication of the pilot operating the helicopter erratically or attempting a descent to land. Therefore, it was unlikely that the pilot had experienced a medical event during the flight.
This analysis will discuss the likely reasons for the accident, the maintenance human factors issues of tracking tasks and workload, and organisational factors related to the quality assurance of the maintenance practices.
Loss of control and in-flight break-up
The condition of the tail rotor driveshaft indicated the tailcone was severed under normal engine power and rotor speed conditions. During a photographic review of the wreckage evidence, the ATSB noted the rear fastener for the cyclic assembly horizontal push-pull tube, which connected it to the bellcrank, was missing. All other bellcrank fasteners were in situ, and correctly assembled. The bellcrank and a bolt, believed to be from the missing fastener, were then recovered from the wreckage for examination.
The heat damage to the bolt, and lack of cadmium residue surrounding the bellcrank bolt hole, indicated the fastener was not fitted during the fire. In addition, the deformation of the bellcrank plates at the location of the missing fastener indicated the fastener was not fitted when the yoke and bellcrank were bent. Further, there was no damage to the bolt or bellcrank bolt holes to indicate the bolt was forcibly removed during the accident sequence. Therefore, it was concluded the bolt had separated from the bellcrank before impact. The absence of the fastener would have resulted in a disconnection of the longitudinal cyclic control. This in turn would have allowed the main rotor disc to tilt aft beyond the normal operating limits (rigging limits), striking the tailcone. Therefore, the severed tailcone was consistent with the separation of the longitudinal cyclic control in forward flight conditions.
The separation of the longitudinal cyclic control would result in the pilot losing pitch control of the main rotor disc. It was very likely that this occurred with little or no warning to the pilot, as there was no indication in the GPS data of an attempted landing. In addition to the loss of pitch control, the severed tail rotor driveshaft would have resulted in the pilot losing directional control. The impact damage and lack of ground witness marks from the main rotor blades, indicated that the helicopter broke-up in-flight.
Therefore, the loss of cyclic control was considered unrecoverable and was consistent with the helicopter colliding with the ground with a very high deceleration after the tailcone was severed.
Separation of the bolt
On consideration as to why the bolt had separated from the cyclic control bellcrank assembly, the ATSB had considered that the self-locking nut failed due to (1) over-torqueing, (2) fatigue cracking, (3) hydrogen embrittlement, (4) loosening, or (5) it was either not installed or was inadequately torqued. The most likely scenario was that the self-locking nut was either not reinstalled or was inadequately torqued.
Over-torqueing
The recovered bolt did not exhibit any damage (elongation) to the grip or threads to indicate it was exposed to excessive torque. Therefore, failure of the nut from over-torqueing was considered very unlikely.
Fatigue cracking
For the bellcrank, the design of the assembled joint is such that loads experienced by the fastener are predominantly a combination of tension within the bolt from axial preload of the joint as the nut is torqued to specification, shear loading of the bolt from operation of the cyclic, and high and low frequency dynamic loading from the rotor system, engine and other rotating components. In each case, the nut is under compression, rather than tension, predicating the likelihood of a nut failure by fatigue to be unlikely.
Hydrogen embrittlement
There have been several previous instances of self-locking nuts found cracked due to hydrogen embrittlement. In 2014, Robinson Helicopter Company released a service letter, which introduced the replacement by attrition of existing MS21042L-series and NAS1291-series nuts with D210‑series corrosion‑resistant nuts. However, in this case the evidence did not support hydrogen embrittlement as a failure mechanism of the missing nut due to the following:
The known batches of affected nuts were Airfasco, and the markings on the nuts installed on VH-HGU were not consistent with this manufacturer.
VH-HGU had been manufactured in 2008, prior to the manufacture of the affected batches of nuts in 2009 and 2010.
The nuts fitted to the bellcrank of VH-HGU had been in service for many years. Delayed hydrogen embrittlement generally occurs in the order of days and weeks, not years. In this time, the maintenance schedule meant there were many opportunities where the nuts would have been visible for inspection.
None of the remaining nuts on the bellcrank, or from the same manufacturer in other locations, exhibited any evidence of cracking associated with hydrogen embrittlement.
Therefore, failure of the self-locking nut from hydrogen embrittlement was considered very unlikely.
Loosening
While the repeated re-use of a self-locking nut could result in degradation and loss of its self‑locking capability, Cloncurry Air Maintenance (CAM) staff were aware of the limitation on their re-use, specifically that they could not be re-used if they had lost their friction torque. Previous work by the ATSB found that a MS21042L-series self-locking nut could be re-used up to 15 times without compromising the friction torque. The cyclic control is not disassembled during the 100‑hour inspection as the non-destructive inspection of parts is only performed at the 2,200-hour overhaul. If the bellcrank was disassembled at each 2,200-hour overhaul, then the nut would only have been re-used twice since production. So while it is possible that the nut had been re-used during the service life of the helicopter, separation of the bolt from the bellcrank from loosening of the nut as a result of a loss of torque in-service was considered unlikely.
Not installed or inadequately torqued
The bolt and bellcrank were found at the accident site and neither exhibited any physical evidence to indicate the fastener may have been predisposed to premature failure. The evidence indicated that the bolt was not installed in the bellcrank at the time of impact, which was about 3 minutes after take-off. It was therefore likely that the self-locking nut was either not installed, or that it was inadequately torqued, at the time of take-off. As it is not possible that there could have been ongoing operation of the helicopter with the nut not attached to the fastener, the most likely reason that the nut was either not installed or inadequately torqued on the accident flight, was due to the maintenance activities that were conducted during the previous 2,200-hour overhaul, completed 2 days prior to the accident.
The maintenance personnel could not recall the details of their work performed on the helicopter. However, they indicated that the bellcrank fasteners would not normally be disturbed when removing the cyclic assembly. Further, although there was no maintenance recorded to indicate that the fastener was disturbed during the overhaul, there were several reasons why the fastener may have been disturbed.
The possible reasons for disturbance of the fastener included inadvertent disassembly to separate the horizontal push-pull tube from the bellcrank, disassembly to measure play in the rod-end with a dial test indicator, or disassembly to adjust the length of the horizontal push-pull tube during the flight control rigging process. There were no records of any of these disturbances in the work‑pack. However, the ATSB noted that disturbances of the flight controls were not recorded in the work-pack, except for the standard overhaul requirements and for the replacement of parts.
The work-pack recorded several certifications for inspections. These inspections would have provided maintenance personnel with the opportunity to observe the bellcrank assembly. It could not be determined why none of these inspections detected an anomaly with the bellcrank fastener.
However, it was noted that the organisation’s maintenance practices relied significantly on human memory. The chief engineer and the head engineer both reported that after they conducted their inspections, they would provide a list of corrective actions. As these defects and corrective actions were not being tracked in the work-pack, and the maintenance staff were carrying a significant workload in the month leading up to the accident, their practices were considered to be conducive to a memory-related error event. These factors are discussed further in the following sections.
Maintenance practices
The 2,200-hour overhaul was the largest scope of maintenance activity for an R22 helicopter. It involved the disassembly of the helicopter, inspections and replacement of a significant number of parts with new or overhauled parts, and reassembly of the helicopter. A ground check and run up is required before the disassembly to capture any additional work for the overhaul. A 100-hour inspection, ground check, run up, track and balance, flight check, and weight and balance are conducted after reassembly and before return to service.
In order to track the progress of work, the CAM Maintenance Procedures Manual (MPM) required all tasks to be progressively certified. That is, certified at the time each item of work was completed. For VH-HGU, the aircraft worksheets were all certified at the end of the overhaul period, on 31 July 2017. Additional disturbances of the flight controls for adjustments and inspections were not recorded. Therefore, without recording all tasks and practicing progressive certification, the work‑pack was not an accurate record of the condition of the helicopter while under maintenance, or of all the work performed on completion of the overhaul.
In addition to the normal certification, any disturbance of the flight controls required an independent inspection. This required the inspector to verify that the work was carried out in accordance with the approved maintenance data and check that the system functioned correctly. The certification for independent inspections was not dated, but considered likely to be 31 July 2017 as it was the last entry in the aircraft worksheets. If it was on this date, then the helicopter was operated for the track and balance, autorotation RPM check and local area flight, without certification for independent inspections. As the disturbances of the flight controls for adjustments were not recorded in the work-pack, the integrity of the independent inspection process was reliant on informal methods of communicating additional work requirements and reporting their completion for re-inspection.
The work-pack included the 100-hour inspection, for which CAM had introduced an abbreviated checklist where a single certification could apply up to 30 separate inspection items. There were no dates recorded for the certifications, but they likely occurred on 31 July 2017. This suggested the checklist was not used to track the 100-hour inspection tasks and manage any interruptions during the process.
When the ATSB reviewed work-packs from other maintenance activities in 2015 and 2016, and the observations made by the Civil Aviation Safety Authority (CASA) audit of 2018, it was apparent that the maintenance documentation practices for VH‑HGU were not an isolated case. The evidence suggested a systemic issue within CAM of not using the maintenance documentation to track the condition of helicopters while under maintenance and to record all maintenance activities.
The use of work-packs at CAM was consistent with the culture of recording and certifying for maintenance for oversight purposes, rather than for quality control in accordance with their MPM. Circumventing the quality control procedures may render them ineffective as a means for ensuring all tasks have been completed correctly.
Extended periods of time between performing and certifying for tasks increased the likelihood of an individual’s memory being subject to source misattribution or suggestibility, or combination of both, when the certification was made. Omissions to record and capture all flight control disturbances in the work-pack increased the likelihood of a prospective memory error during the overhaul period. Therefore, the maintenance practices at CAM exposed the organisation to an increased risk of memory‑related errors and the omission of tasks.
Organisational structure and workload
In the period 2013 to 2017, the CAM workforce structure changed from a majority of licenced aircraft maintenance engineers to three apprentices with one aircraft maintenance engineer and two licenced aircraft maintenance engineers. CAM undertook maintenance for CMC helicopters as one part of its operation, as well as maintenance of helicopters from external operators as another part. With one licenced aircraft maintenance engineer and apprentice assigned to the external helicopters, and one apprentice attending trade school in the period leading up to the accident, there were effectively three members of staff for the CMC helicopters (chief engineer, aircraft maintenance engineer and a fourth-year apprentice).
Further, the structure of the workforce required the chief engineer to assume responsibility for the planning, supervision and coordination of maintenance for the CMC jobs. When the ATSB attempted to obtain details about the maintenance of the cyclic assembly on VH-HGU, the staff consistently reported that they could not recall specific details, and that it was a busy period with the overhaul constantly interrupted for 100-hour inspections. The month leading up to the accident included 20 100-hour inspections on CMC helicopters, which was consistent with the staff reports of it being a busy period.
The ATSB used a labour-hour plan to review the CAM staffing levels over this period and established that 100-hour inspections should have taken about 480 labour-hours. This equated to a requirement for three full-time qualified staff members, in addition to what was required to progress the overhaul for VH-HGU.
The volume of work and turn-around times were consistent with the peak mustering season and the staff reports of regular interruptions to the overhaul for other jobs. If the workforce structure does not change as the production requirements increase, it is likely that junior personnel will be allocated more responsibilities. This may occur concurrently with less supervision if the supervisor’s workload must also increase to deliver the production goals.
Therefore, the volume of work and interruptions to the overhaul in the month of July 2017, combined with the low levels of staff experience and qualifications, and maintenance practices, increased the risk of a maintenance error event. In addition, the intensity of the work likely reduced the chief engineer’s capacity to effectively supervise all the activities related to the CMC helicopters.
Internal independence
The CMC-CAM managing director was the CASA approved Head of Aircraft Airworthiness and Maintenance Control. This position is intended to provide an interface with maintenance organisations for the planning and preparation of maintenance activities, and an independent check of the completion of those activities.
The managing director, who had a pilot background, had delegated the Head of Aircraft Airworthiness and Maintenance Control responsibilities to the position of maintenance coordinator, which was filled by the chief engineer at the time of the accident. This decision resulted in the same individual holding the two key positions of airworthiness and maintenance management within CMC and CAM. As a result of this structure, the chief engineer had a considerable number of responsibilities and there was no independent assurance of maintenance quality from the Air Operator Certificate holder. In addition, there was no requirement for CAM to have a quality manager to routinely monitor, measure and evaluate the organisation’s performance, and advise the managing director and chief engineer of the results.
In the absence of an independent maintenance coordinator or quality manager, the organisation was operating with very few checks and balances. In addition, the ATSB noted that all maintenance staff, including the chief engineer, were trained through their apprenticeships at CAM. The home‑grown workforce, combined with no permanent internal independent oversight, limited CAM’s exposure to alternative maintenance practices and continuous improvement.
Audit oversight
In the absence of a quality manager for CAM, the role of internal audit was managed by contracting an external auditor. The ATSB reviewed the two internal audits performed in 2015 and 2016, and noted there were no findings, no requests for corrective action and no suggestions for improvements. Upon review of the work-pack sampled in the 2016 audit, the ATSB noted there was no evidence of progressive certification, an abbreviated 100-hour inspection checklist was used, and a single certification was made for the entire 100‑hour inspection on the airframe, ground check and run up.
The observations of the sampled work-pack suggested it was not used to track the progress of maintenance, which presented the risk of the omission of inspections during periods of interruptions. In contrast, the Robinson Helicopter Company maintenance manual checklist for the 100-hour inspection provided points of certification for each item. Chapter 6 of the CAM MPM included the requirements to conduct maintenance in accordance with approved data and to progressively certify for each item as it is completed. Use of the Robinson Helicopter Company checklist would have provided the auditor with evidence that approved data was used and current, and that it facilitated progressive certification, thereby demonstrating that requirements were being met.
Similarly, in 2015, CASA performed their last system-based audit of CAM prior to the accident. The auditor sampled three work-packs, which included a 2,200-hour overhaul for an R22, with no issues identified. The reported criteria for the sampling was Chapter 6 of the CAM MPM. The ATSB’s review of that work-pack found that it did not capture all the requirements of the overhaul procedure or progressive certification. Therefore, it did not conform to Chapter 6 of the MPM. However, a post-accident audit conducted by CASA identified a number of findings similar to those observed by the ATSB.
From the ATSB’s review of the sampled work-packs, it was noted that the maintenance practices employed by CAM during the overhaul of VH-HGU were present before the helicopter was acquired by CMC in February 2017 and entered overhaul. These practices were visible to auditors engaged in internal and external audits of CAM and indicated that the work-packs were not being used for progressively recording and tracking tasks. Consequently, the audits were missed opportunities to identify and recommend improvements to the practices employed by CAM staff, which limited their benefit to CAM as a quality assurance tool.
Re-use of self-locking nuts
In the course of interviewing personnel employed by CAM, the ATSB noted a low level of awareness of the need to replace MS21042L/NAS1291-series nuts with the D210-series nuts when critical fasteners were reassembled. In accordance with the R22 maintenance manual, critical fasteners include a self-locking nut in their assembly. It is a standard practice within sectors of the aviation industry to re-use self-locking nuts provided the nut cannot be turned onto the bolt thread by hand and the published torque value for the fastener is achieved.
In December 2018, the ATSB received the accident helicopter’s jackshaft, which had the fasteners attached. The jackshaft was one of a number of parts within the flight control system that was disassembled and sent for non-destructive inspection during the 2,200-hour overhaul. In late January 2019, the ATSB completed semi-quantitative chemical analysis of the nuts fitted to the jackshaft and found they were consistent with a carbon/alloy steel, and therefore not consistent with D210-series stainless steel corrosion-resistant nuts.
At the time of the reassembly of the accident helicopter, the current R22 Illustrated Parts Catalog detailed the part number D210-4 for the nuts fitted to the jackshaft, and RHC confirmed there was no alternate part number to the D210-series nuts. Therefore, the ATSB concluded that the industry practice of re-use of self‑locking nuts on Robinson helicopters may result in the omission to install D210-series nuts when critical fasteners are reassembled.
Findings
From the evidence available, the following findings are made with respect to the loss of control and in-flight break-up involving the Cloncurry Mustering Company Robinson R22 helicopter, registered VH-HGU, 7 km north-north-west of Cloncurry Airport, Queensland, on 2 August 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
About 3 minutes after take-off, a bolt separated from the cyclic control bellcrank, which resulted in an unrecoverable loss of control, in-flight break-up and collision with terrain.
The bolt separated from the bellcrank during flight, likely due to either the self-locking nut not being reinstalled or inadequate torque of the nut on completion of the 2,200-hour overhaul. The accident flight was the first commercial flight after the 2,200-hour overhaul.
Other factors that increased risk
Cloncurry Air Maintenance had adopted a number of practices, which included using abbreviated inspection checklists, not recording all flight control disturbances and not progressively certifying for every inspection item as the work was completed, which increased the risk of memory-related errors and the omission of tasks. [Safety Issue]
The number of helicopters for which maintenance was performed in the month leading up to the accident likely exceeded the workforce capability, given the staffing levels and qualifications. This likely reduced the capacity of the chief engineer to conduct oversight activities and increased the risk of a maintenance error not being captured.
Cloncurry Air Maintenance had limited internal independent oversight and increased reliance on audits for the evaluation of its quality performance. This was partly due to:
the absence of an independent maintenance coordinator or quality manager, and
all maintenance staff had worked almost exclusively for Cloncurry Air Maintenance, which limited the organisation's exposure to other maintenance practices.
The most recent contracted audit of Cloncurry Air Maintenance, performed as part of the organisation's quality activities, and the previous audit conducted by the Civil Aviation Safety Authority, did not provide any observations of error-conducive maintenance practices, although they were present at the time. These were missed opportunities to identify and recommend improvements to the tracking and certification of maintenance tasks.
During reassembly of the helicopter after the 2,200-hour overhaul, self-locking nuts, consistent with MS21042L-series nuts, were re-used on critical fasteners without replacing them with D210-series corrosion resistant nuts in accordance with the manufacturer's instructions for continued airworthiness. The D210-series nuts were introduced to reduce the risk of hydrogen embrittlement cracking from the MS21042L-series and NAS1291-series nuts.
Other findings
There was no recorded maintenance on the helicopter to indicate that the bellcrank fastener was removed, and it was not always necessary to disassemble it during the 2,200-hour overhaul. However, there were several reasons why it could have been disturbed. These included disturbance as part of the disassembly of the cyclic control assembly, disassembly to inspect the attached rod-end with a dial test indicator, or disassembly to adjust the length of the horizontal push-pull tube as part of the main rotor rigging process. However, based on the evidence available, the ATSB could not establish if any of these tasks were performed.
On completion of the helicopter's 2,200-hour overhaul, there were several certifications for inspection of the cyclic control assembly. The reason why these inspections did not detect an anomaly with the cyclic bellcrank fastener could not be determined.
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: Cloncurry Air Maintenance had adopted a number of practices, which included using abbreviated inspection checklists, not recording all flight control disturbances and not progressively certifying for every inspection item as the work was completed, which increased the risk of memory-related errors and the omission of tasks.
Additional safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence:
Australian Transport Safety Bureau
ATSB safety advisory notice to maintenance personnel for Robinson helicopters
In March 2019, the Australian Transport Safety Bureau issued a safety advisory notice advising all Australian maintenance personnel for Robinson helicopters to ensure that before re-using a self-locking nut, that the correct part number is fitted, and that the D210-series corrosion-resistant nuts are used for reassembly of critical fasteners in accordance with the Robinson Helicopter Company instructions for continued airworthiness.
On 5 June 2019, the Civil Aviation Safety Authority released airworthiness bulletin (AWB) 67-005 Issue 1: Robinson Helicopter Flight Controls – Duplicate Inspections [independent inspection]. The purpose of AWB 67-005 was to advise all operators and maintainers of the need to replace MS2104 hardware during removal or replacement of such hardware and the requirement to complete a duplicate inspection of each stage of maintenance on the primary flight controls.
On 20 June 2019, the Civil Aviation Safety Authority released AWB 67-005 Issue 2: Robinson Helicopter Flight Controls – Independent Inspections. Issue 2 highlighted the need for independent inspections to be conducted and ‘recorded consecutively with each adjustment made during rotor tracking and balancing’ activities. In addition to several recommendations, Issue 2 identified several human factor elements that could impact inspection performance, and highlighted the need for extra caution during post-maintenance flights in accordance with Robinson Helicopter Company safety notice SN-43:
…any work completed on the flight control system deserves special attention because a flight control disconnect is almost always catastrophic.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Civil Aviation Safety Authority
Cloncurry Air Maintenance
Cloncurry Flinders Medical Centre
Cloncurry Mustering Company
Ergon Energy
Pilot’s next-of-kin
Queensland Department of Health
Queensland Police Service
Robinson Helicopter Company
United States National Transportation Safety Board.
References
Australian Transport Safety Bureau 2019, AO-2016-156: In-flight break-up involving Robinson R44, VH-ZNZ, 41 km NW Mossman, Queensland, 18 November 2016, ATSB, Canberra.
Australian Transport Safety Bureau 2014, AO-2011-135: Embrittled nut and related failures Robinson R22 Beta helicopter, VH-JNP, 22 km N of Saxby Downs, Queensland, 12 October 2011, ATSB, Canberra.
Australian Transport Safety Bureau 2012, AO-2011-016: Loss of control, Robinson Helicopter R44 Astro, VH-HFH, Cessnock Airport, New South Wales, 4 February 2011, ATSB, Canberra.
Australian Transport Safety Bureau 2008, AR-2008-055: An Overview of Human Factors in Aviation Maintenance, report prepared by A Hobbs, Canberra.
Dismukes, K and Nowinski, J 2007, ‘Prospective memory, concurrent task management, and pilot error’. In AF Kramer, DA Wiegmann and A Kirlik (Eds.), Series in human-technology interaction. Attention: From theory to practice (pp. 225–236), Oxford University Press.
National Aerospace Standard, NAS6603 thru 6620, Bolt, tension, hex head, close tolerance, alloy steel, long thread, reduced major dia., self-locking and non-locking, 160 KSI Ftu, Revision 8, June 12, 2009.
Schacter, LD 1999, ‘The seven sins of memory: Insights from psychology and cognitive neuroscience’, American Psychologist, vol. 54, no. 3, pp. 182-203.
United States National Transportation Safety Board 2013, NTSB/AAR-13/01: Loss of Control, Sundance Helicopters, Inc. Eurocopter AS350-B2, N37SH, Near Las Vegas, Nevada, December 7, 2011, NTSB, Washington.
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the Civil Aviation Safety Authority, Cloncurry Air Maintenance and Cloncurry Mustering Company personnel, pilot’s next-of-kin, pilot’s designated aviation medical examiner, Queensland Department of Health, Queensland Northern Coroner, Robinson Helicopter Company and the United States National Transportation Safety Board.
Submissions were received from the Civil Aviation Safety Authority, Cloncurry Air Maintenance and Cloncurry Mustering Company, pilot’s next-of-kin, pilot’s designated aviation medical examiner, Queensland Northern Coroner and the Robinson Helicopter Company. The submissions were reviewed and where considered appropriate, the text of the draft report was amended accordingly.
Appendices
Appendix A – Materials examination report
Introduction
Following a review of the site images for the wreckage of VH-HGU and impact information, a critical fastener from the cyclic control system was identified to be missing. The cyclic is one of the primary controls that a pilot must use during flight. It allows flight to be controlled in any direction of travel by tilting the main rotor disc. The cyclic stick within the R22 cabin was coupled to a non‑rotating swashplate by a mechanical linkage comprising push-pull tubes, pivots, a bellcrank and its associated fasteners (e.g. bolts and nuts, rod ends, spacers and washers). The underfloor bellcrank provided the linkage between the horizontal and vertical push‑pull tubes. It transmitted horizontal push-pull tube movement to vertical movement that tilted the swashplate, producing an associated tilting of the main rotor disc.
The missing fastener was normally installed in the bellcrank, connecting through the rod end of the horizontal push-pull tube (Figure A1). Due to the criticality of this fastener in relation to the operation of the cyclic control and its absence predicating an in-flight loss of control, several items from the wreckage were recovered from the accident site. The retained items were examined in closer detail at the ATSB’s technical facilities in Canberra. They included:
bellcrank (part number A958-1) and associated componentry
recovered pieces of metallic debris
jackshaft (part number A337-1) and associated componentry
a single NAS6604-15 bolt
additional loose nuts and washers
forward support assembly (part number A014-6).
Figure A1: View looking upwards of an exemplar R22 control system, showing the bellcrank and location of the missing fastener
Source: ATSB
Scope
The scope of the examination was to analyse the bellcrank, yoke, and related components to determine how the fastener came to be missing, and to examine the pieces of metallic debris to determine if any additional components could be recovered. The jackshaft shared the same fastener type as the bellcrank assembly and was examined for comparative purposes. Additionally, the forward support assembly was used to verify the presence and security of NAS6604-15 bolts.
Examination
Bellcrank fasteners
The missing bellcrank fastener was an assembly of components comprised of the following (Figure A2):
NAS6604-15 bolt
NAS1149F0432P washer
A115-1 spacer
B332-441 lockwasher
D210-4 nut
rod-end.
Figure A2: Modified image from the R22 Illustrated Parts Catalog showing missing fastener assembly components and location
Source: Robinson Helicopter Company, annotated by the ATSB
Specified bolt
The current Robinson Helicopter Company (RHC) R22 Illustrated Parts Catalog (IPC) showed that the horizontal and vertical push-pull tubes from the cyclic control assembly were required to be attached to the bellcrank with a National Aerospace Standard (NAS) 6604-15 bolt[43] and D210-4 nut. The NAS specification listed the material type as alloy steel, grade 4140, 4340, or 8740. Table A1 provides the bolt dimensions from that specification.
Table A1: NAS6604-15 bolt specifications
Bolt
Thread UNJF-3A
Width (flats) (in)
Shank diameter (in)
Thread length (in)
Grip length (in)
Length (in)
Height (head) (in)
NAS6604-15 bolt
0.2500-28
0.429- 0.439
0.2485- 0.2495
0.425
0.938
1.363
0.125
Specified nut
Prior to 2014, the specified nut was an MS21042L-series or NAS1291-series. However, RHC issued a R22 service letter SL-64, D210 Corrosion-Resistant (CRES) nuts, on 13 October 2014, which addressed potential cracking of MS21042L-series nuts.
The D210-series CRES nuts, which supersede MS21042L-series and NAS1291-series nuts, are not susceptible to cracking. The service letter directed that when performing maintenance that involved disassembly of a critical fastener (joints with a secondary lock), the fastener should be reassembled using a D210-series nut. The IPC was updated in February 2017 to reflect these changes. Table A2 provides the dimensions of the nuts.
The recovered bellcrank remained attached to the torque tube yoke assembly, which had fractured at the termination of the attached stiffening brackets. The submitted assembly exhibited significant damage as a result of mechanical and heat effects. All remaining rod ends, including those attached to the vertical push-pull tubes and collective fork assembly, had fractured in overstress (Figure A3).
Figure A3: Side view of the bellcrank as received, location of missing fastener circled
Source: ATSB
The torque tube yoke assembly had separated from the bolt for the lateral cyclic vertical push-pull tube rod end on the left side, and was distorted from a combination of mechanical impact and heat. The left side of the yoke assembly exhibited significant distortion, and had been plastically deformed inward, towards the right side. The left bellcrank plate had been distorted in a similar way, causing the two plates to come together at the location of the missing fastener. The yoke assembly also exhibited heat damage in this area, with the left side moulding around the bellcrank plate (Figure A4).
Figure A4: Side view of the bellcrank as received showing deformation of yoke and plate
Source: ATSB
Following initial visual examination and photography, the bellcrank was removed from the torque tube yoke assembly for further examination. The bellcrank exhibited distortion from a combination of mechanical stress and heat effects. The two plates of the bellcrank had been deformed along the length between the vertical push-pull tube and torque tube attachment ends (Figure A5). Where the fasteners remained in position, the two plates had deformed in parallel. However, as above, where the fastener was missing, the two plates of the bellcrank had been pushed closer together.
Figure A5: Bellcrank following removal from the torque tube and showing parallel deformation of both plates
Source: ATSB
Closer examination of the bellcrank plates showed that a yellow residue had been deposited around the holes where the bolts had been in position. However, there was minimal residue around the hole where the fastener was missing (Figure A6). The manufacturer advised the residue was likely cadmium plating from components within the fastener assembly that had melted during the fire. They were also of the opinion that the minimal residue observed around the hole where the fastener was missing was likely from cadmium plating transfer from a previous installation. The presence of cadmium within the residue was confirmed by semi-quantitative chemical analysis using a scanning electron microscope (SEM) equipped with an Oxford energy dispersive x-ray spectrometer (EDS).
Figure A6: Bellcrank internal surfaces showing the cadmium plating residue
Source: ATSB
There was no evidence of deformation or elongation of the bellcrank fastener hole to suggest that the nut and bolt had detached forcefully during the collision. The surface of the bellcrank in the region adjacent to the missing bolt, and the internal surface of the bolt hole, was rippled as a result of high temperatures associated with the fire. Minor damage in the form of scrapes and dents were observed in the region adjacent to the bolt hole of the missing fastener, coincident with where it had been in contact with the torque tube yoke assembly (Figure A7).
Figure A7: Comparison between the bolt hole where the fastener was missing (left) showing deformation due to heat and a bolt hole where a fastener remained in position (right)
Source: ATSB
An exemplar bolt could not be inserted through the bellcrank bolt holes where the fastener was missing. This was due to a combination of misalignment of the two plates as a result of impact damage, and the heat damage observed on the internal surfaces of the holes.
Remaining bellcrank bolts
Markings on heads of the two remaining bolts from the bellcrank indicated they were a NAS6604‑15 bolt. The marking ‘LFC’ stamped on the bolt head identified the manufacturer (Figure A8). As per United States Department of Defence Handbook, MIL-HDBK-57G (IS) 16 October 2012, Listing of Fastener Manufacturer’s Identification Symbols, the manufacturer was likely to be: LFC Industries, Texas, USA.
Figure A8: Bolt head markings from one of the remaining bellcrank bolts
Source: ATSB
Remaining bellcrank nuts
The nuts of the two remaining fasteners were stamped with an ’R’ symbol on two of the hexagon flats on opposite sides. As per United States Department of Defence Handbook, MIL-HDBK-57E Listing of Fastener Manufacturer’s Identification Symbols, the nuts were most likely manufactured by Ronson Manufacturing Inc. (Figure A9). The two remaining nuts were in relatively good condition, with no evidence of any cracking or damage observed. The chemical analysis results, provided in Table A3, confirmed the nuts were manufactured using 4037 alloy steel. Measurements and chemical analysis confirmed that they were consistent with MS21042‑L4/NAS1291-series nuts.
Figure A9: Nut markings from one of the remaining fasteners (left) and relevant page from MIL-HDBK-57 showing manufacturers marks (right)
Source: ATSB
Table A3: Chemical analysis results for a nut removed from the bellcrank
Specification
Fe
C
Mn
Si
S
P
Ni
Cr
Mo
Cu
V
Al
Bellcrank nut
Bal
0.39
0.75
0.26
0.01
0.01
0.05
0.19
0.23
0.12
0.01
0.023
Alloy 4037
-
0.35-0.40
0.70-0.90
0.15-0.35
0.04
0.35
-
-
0.20-0.30
-
-
-
Units are weight %
Additional recovered bolt
The bolt found on 16 May 2018 by the pilot’s next-of-kin displayed the same markings as those that remained in position on the bellcrank (NAS6604-15 manufactured by LFC) (Figure A10). The surfaces of the bolt were severely heat affected, with areas of material loss and areas where additional material had adhered to the surface. Ultrasonic chemical cleaning of the bolt was unable to remove much of the adhered material. There was no damage observed to the head, shank or threads of the bolt. A dial indicator was used to check the bolt run-out, which confirmed it to be straight without significant distortion along the length.
Figure A10: NAS6604-15 bolt found 16 May 2018
Source: ATSB
Closer examination of the bolt threads confirmed significant heat damage, and a small groove located on the second to third threads from the end of the bolt (Figure A11). Other than the small groove, the bolt threads did not show any other markings such as grooves, score marks or galling.[44] A similar marking was observed on the other bellcrank bolts. This indicated that a nut had been installed at some point on the examined bolt. The bolt was examined using a scanning electron microscope equipped with an Oxford energy dispersive x-ray spectrometer. No evidence of remnant cadmium plating was detected on the bolt surfaces.
Figure A11: Magnified image of the NAS6604-15 bolt found 16 May 2018 showing thread groove
Source: ATSB
Radiography of metallic debris
Aluminium alloy portions of the helicopter had melted during the post-accident fire and then resolidified into blobs of metallic debris. The debris was gathered from the wreckage and submitted to the Australian National University for radiography[45] to determine the presence of entrapped hardware (e.g. nuts, bolts, washers) that may have been similar in size or shape to the components from the fastener assembly missing from the bellcrank.
While some samples did show evidence of steel componentry, including nuts and bolts, within the solidified metallic debris, nothing was identified that was similar in size or shape to a NAS6604-15 bolt, D210-4 nut, or MS21042-L4/NAS1291-series nuts. The fasteners identified were too long or short, threaded the entire length, were a complete assembly (nut was still attached), had a different shaped head or were attached to other componentry (Figure A12).
Figure A12: One of the metallic pieces recovered from the accident site and the corresponding radiograph that highlighted the presence of entrapped steel hardware
Source: ATSB (left) and Australian National University (right)
Dissolution of metallic debris
Following the suspected recovery of the missing bolt from the bellcrank, an internal technical review of the radiography questioned if that technique was capable of resolving a small part, such as a D210-4 or MS21042-L nut. When taking into account potential for hydrogen embrittlement and cracking of the MS21042-L series nuts, it was considered that, if the nut had fractured into thirds, it may not have been visible on the radiographs. As such, the metal pieces were dissolved in a caustic soda (sodium hydroxide) solution. The resulting solution was sieved using a 352 mesh (minimum captured particle size of 1.5 mm) to recover the entrapped hardware.
A number of fasteners and other components were recovered following dissolution of the aluminium (Figure A13). The missing nut to the bellcrank fastener was not amongst the entrapped hardware. Neither a D210-4 nor MS21042-L series (whole or in part) nut was among the recovered items.
Figure A13: Recovered items following dissolution of the metallic debris
Source: ATSB
Additional hardware
Additional hardware was received in June 2018 by the ATSB, which included:
additional fastener parts (four small bags of nuts and washers)
forward support assembly (part number A014-6) with two NAS6604-15 bolts.
The samples were examined to identify the fastener designations, verify that the NAS6604-15 bolts were installed and to determine if any of the nuts may have been the missing nut.
The received nuts were examined in the ATSB laboratories with the measurements and observations recorded (Table A4). Due to fire damage, some of the markings on a number of the nuts were unable to be determined.
‘c’ and ‘k’ on basevertical line on opposite flats
The forward support assembly (A014-6) was part of the landing gear, and the IPC showed that it should contain two NAS6604-15 bolts.[46] Due to fire damage, the markings on the heads of the two bolts from the forward support assembly were illegible. However, the bolts were measured and the results consistent with the requirements for a NAS6604-15 bolt Table A5.
Table A5: Results from bolt examinations
Width (flats) (in)
Shank diameter (in)
Thread length (in)
Grip length (in)
Length +/-0.015 (in)
Height (head) (in)
NAS6604-15 bolt
0.429- 0.439
0.2485- 0.2495
0.425
0.938
1.363
0.125
A014-6 bolts
11.16mm (0.439in)
0.249
0.429
0.935
34.74mm (1.368in)
0.126
Jackshaft
Maintenance records showed that the jackshaft had undergone maintenance, including non‑destructive testing, on or around 25 May 2017 during the 2,200-hour overhaul. The testing involved the removal of the fasteners, and as per the R22 service letter SL-64, updated IPC and maintenance manual, the nuts on the jackshaft should have been changed to the new D210‑series nuts at this time.
Examination of the four nuts showed them to be similar to those remaining in the bellcrank. Specifically, they were of a similar size, and three of them exhibited the same markings ‘R’ on the flats (Figure A14). Due to heat damage, no markings were able to be resolved on the fourth self-locking nut. Analysis of the four nuts from the jackshaft assembly was performed using the EDS and showed that all four nuts were consistent with a carbon/alloy steel, not stainless steel. The geometry, markings and chemistry indicated they were MS21042-L4/NAS1291-series nuts.
Figure A14: Jackshaft assembly (left) and magnified view of one of the nuts (right)
Source: ATSB
Discussion
Separation of the fastener from the bellcrank
The investigation considered when separation of the fastener from its installed position within the bellcrank was likely to have occurred. A number of observations indicated that the fastener was not in position at the time of the impact with the ground:
There was an absence of significant physical damage to the bolt holes where the bolt was missing and surrounds. That is, no gross deformation or elongation of the holes to indicate that the fastener assembly had been forcibly removed during the accident sequence.
The bellcrank and torque tube fork assembly had been subject to significant mechanical damage such that the rod ends had fractured in overstress and the left side of the yoke assembly and bellcrank plate had significantly distorted. While the distortion of the plates was similar where the fasteners remained in position, the plates had been pushed together where the fastener was missing.
Rippling was observed on the internal surfaces of the bolt hole, considered to be evidence of heat damage, and the bellcrank was twisted/distorted such that a new bolt was unable to be inserted into the hole. The two remaining bolts could be easily reinserted into their respective holes following removal.
Yellow colouration was present on the inside of the bellcrank around the two fasteners that had remained in position. This was likely from the oxidised cadmium plating from the installed hardware including nuts, bolts and washers. No such colouration was observed around the internal surfaces of the bellcrank holes where the fastener was missing. This indicated that the bolt and associated hardware was not in position at the time of the post-impact fire. A minimal amount of residue was observed around the hole on the nut side of the bellcrank, likely from material transfer from the lock washer. This suggested the fastener had been previously installed.
Bellcrank – the missing fastener
A solitary bolt excavated from the accident site and submitted by the next-of-kin exhibited the markings of a NAS6604-15 bolt. It also exhibited the same manufacturing mark as that on the other bolts fitted to the bellcrank. As all the other NAS6604-15 bolts were accounted for—on the bellcrank, forward support assembly, main rotor head yoke assembly and inside main rotor blades —it was very likely that this was the missing bolt from the bellcrank. The bolt was in relatively good condition, and except for thermal effects from the post-accident fire, it showed no damage on the head, shank or threads. One small groove was observed on the second to third thread flank, which was potentially from engagement with a self-locking nut during assembly. There did not appear to have been any galling or thinning of the threads, which is damage that would be expected from multiple installations of a MS21042-L4 nut.
Jackshaft
Examination of the jackshaft assembly recovered from the wreckage of VH-HGU showed that three of the four nuts had the same manufacturer markings to the nuts in position on the bellcrank. There were no discernible markings on the fourth nut. The same manufacturer’s mark was also observed on the forward support assembly, and it was considered very likely that the nuts were original from manufacture.
The ATSB’s chemical analysis of the nuts confirmed that all four were consistent with a carbon/alloy steel. Though the analysis was semi-quantitative, the spectrographs of the four nuts were inconsistent with the CRES (corrosion resistant – stainless steel) D210-4 nuts specified in the Robinson R22 IPC. The nickel, chromium and molybdenum additions, where detected, were not of sufficient quantity to designate the nuts as stainless steel. The nuts fitted to the jackshaft were therefore likely MS21042-L4/NAS1291-series nuts.
Conclusion
The following is a summary of the main findings made during examination of the bellcrank and associated components, other recovered items and the jackshaft from VH-HGU:
Due to the observed damage on the bellcrank and torque tube fork assembly, the horizontal push-pull tube fastener assembly was not in position at the time of the impact with terrain.
The remaining bolts from the bellcrank were consistent with a NAS6604-15 bolt and the nuts were consistent with an MS21042L4/NAS1291-series nut.
The solitary bolt found on 16 May 2018 was consistent with an NAS6604-15 bolt, and had the same manufacturer mark as the bolts that had remained in position. As the other NAS6604-15 bolts were accounted for, it was very likely that this was the missing bolt from the bellcrank.
The self-locking nut from the missing bellcrank fastener assembly was not recovered in the wreckage, including in the pieces of metallic debris when dissolved.
The nuts on the jackshaft assembly were not changed to D210-4-series nuts as per the Robinson instructions for continued airworthiness when they were removed to perform non‑destructive testing on the jackshaft (part number A337-1) during the 2,200-hour overhaul.
Appendix B – Maintenance workload
Figure B1 and Figure B2 depict the progression of the 100-hour inspections (yellow) and 2,200‑hour overhauls (green) by Cloncurry Air Maintenance for the Cloncurry Mustering Company in the month prior to and following the accident (red).
Figure B1: CAM maintenance jobs for CMC in July 2017
Source: ATSB
Figure B2: CAM maintenance jobs for CMC in August 2017
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 31 July 2017, a team of Sydney Trains’[1] infrastructure maintainers were conducting a series of inspections and measurements along the Up and Down[2] Illawarra Main and Up and Down Illawarra Local lines, Tempe. The workgroup were located between 746 points and 748 points when a passenger service 59-J travelling on the Down Illawarra Local line towards Tempe Station narrowly missed the workgroup as it passed their worksite. There were no injuries or damage.
What the ATSB found
The workgroup had relied on lookout working (LOW) as the method of worksite protection. Two workers were positioned as lookouts for oncoming trains; one trackside watching for the approach of Down trains, using track warning lights[3] (Down lookout), the other positioned at Tempe[4] Station footbridge watching for the approach of Up trains (Up lookout). The Down lookout had diverted his attention away from the warning lights to acknowledge an Up train. When he re-focussed on the warning lights, he realised a warning light for approaching Down trains had extinguished. He was not able to sound a warning to the workgroup and give them sufficient time to clear the danger zone to a safe location, before 59-J approached their location.
Additionally, the ATSB found the location of the worksite was considered unsuitable for LOW according to Sydney Trains’ Worksite Protection and Hazardous Locations Register (WPHLR).
What's been done as a result
On 12 November 2017, Sydney Trains made changes to NPR 711 Using Lookouts[5]. Instructions mandated that warning lights must not be used to provide warning of approaching rail traffic when using lookouts. Further, this instruction applied to all tracks in the Sydney Trains Network unless specifically exempted in the Network Local Appendices.
Sydney Trains is also reviewing the WPHLR with a view to simplifying the document by only including locations where LOW is specifically prohibited.
Safety message
Compared to the other worksite protection methods, Lookout Working (LOW) does not warn, or restrict trains from approaching, or entering a work location. Where practicable, rail transport operators (RTOs) must require track workers to continually re-assess the site risks, add/combine safety measures (like Automatic Track Warning System, or audible warning devices), or implement a higher form of protection.
On the morning of 31 July 2017, a team of four Sydney Trains infrastructure maintainers from their Sydenham Network Base gathered to conduct a series of regular inspections and measurements at several points along the Up and Down Illawarra Main and Up and Down Illawarra Local lines, Tempe. The work involved four sets of points, with the incident occurring between 746 points and 748 points (see Figure 1).
Figure 1: Incident location – Tempe, NSW
Source: ATSB
Two workers forming an inspection team, entered the danger zone and accessed the track in accordance with procedures for the protection of track workers using Network Rule NWT 310 Lookout Working. The rules stipulated that all workers and equipment were to be completely within a safe place a minimum of ten seconds before rail traffic entered a worksite (passed their location).
At approximately 1000, empty passenger service 59-J was travelling on the Down Illawarra Local line towards Tempe Station, when the driver observed the workgroup in the danger zone. The driver applied the train brakes, blew the horn and the workers began to move off the line towards a safe place, to the side of the track or ‘cess’ (see Figure 1). A review of CCTV footage from the train showed that the workers had nearly reached a safe place when the train passed the workers’ location (approximately seven seconds after the train first observed the work group). There were no injuries or damage.
The incident involving train 59-J occurred when the Down lookout responded to the horn from the approaching Up train. He turned away from the warning lights to provide an ‘all clear’[6] hand signal to the driver of the Up train. He then waited for an acknowledgement from the driver of the Up train, before turning back to re-focus on the warning lights. He realised a warning light for approaching down trains had already extinguished. He was not able to sound the warning to the work group and give them sufficient time to clear the danger zone to a safe location, before 59-J approached their location.
The incident location at Tempe is approximately 6.5 km from Sydney’s Central Station and is a multiple-track site consisting of the Up and Down Illawarra Main and Up and Down Illawarra Local lines.
Figure 2: Location of Tempe Station, NSW
Source: Google Maps
Worksite protection
Network Rule NWT 300 Planning Work in the Rail Corridor requires work in the danger zone to be planned and carried out using one of five methods of worksite protection[7]. The different methods of worksite protection are implemented according to the risk involved with the work task.
LOW is relatively expedient to implement compared to other worksite protection methods. This is because LOW does not prevent trains from entering the worksite. Protection of workers under LOW is reliant on positive outcomes from human performance and compliance to procedures.
To minimise risk, the Network Rules encourage track workers to assess and reassess the risks at each location, apply additional safety measures, or implement a higher form of protection, where practicable. NWT 300 states that Local Possession Authorities (LPAs) and Track Occupancy Authorities (TOAs) are the preferred methods of working on track, mainly as they authorise closure, or exclusive occupation of the track. The LOW rule, NWT 310, reinforces this philosophy when it states:
‘If Absolute Signal Blocking (ASB) is available, it is preferred over Lookout Working’.
Some considerations in reducing risk when using LOW are to add, or combine, additional safety measures like Automatic Track Warning System (ATWS), or audible warning devices.
LOW network procedure
Lookouts are responsible for maintaining minimum allowable sighting distance, remaining vigilant for and detecting the approach of trains, and for warning workers in the danger zone of an approaching train.
The LOW Network Procedure NPR 711 states lookouts must:
Agree with the Protection Officer on how workers will be warned about the approach of rail traffic.
Stand in a safe place where you can see approaching rail traffic and be within sight and hearing of the workers. If you cannot do both of these safely, tell the Protection Officer.
Keep a continuous lookout for the approach of rail traffic.
When rail traffic approaches, warn the workers immediately.
Only if workers and their equipment are in a safe place, face the approaching train or track vehicle and give the ALL CLEAR handsignal to the Driver or Track Vehicle Operator.
Wait for the Driver or Track Vehicle Operator to acknowledge the ALL CLEAR handsignal.
Make sure that the line is clear before telling the Protection Officer that it is safe for work to resume.
Tell the Protection Officer if you need to move from your designated position. Do not move from your position until: - all workers and their equipment are in a safe place - a new Lookout is in position
Tell the Protection Officer if conditions such as visibility change.
The Network Rules do not stipulate any separate criteria for trains approaching from one direction or another direction.
Location of the Lookouts
The distance of the work group at 746 points from the Up lookout was approximately 350 metres. The distance of the work group from the Down lookout from 746 points was approximately 170 metres. At these locations the Down lookout was within sighting distance of the work group, however, the sighting distance to the Up lookout was obstructed by the overhead bridge stanchions.
Figure 3: View from the position of the Down lookout
Source: ATSB
Figure 4: View from the position of the Up lookout, looking towards the work group
The Worksite Protection Hazardous Locations Register (WPHLR) identifies hazardous locations across the Sydney Trains rail network. Its purpose is to help users understand the hazards relating to worksite protection in these hazardous locations and provide recommendations for implementing appropriate worksite protection.
This section of track was included on the WPHLR and was considered an area inappropriate for using LOW. The Up Main and Down Local Illawarra lines were the two inside rail lines of the four rail line corridor. These tracks were identified to have some areas with inadequate sighting distance or no safe place. The recommended precautions were:
‘Unless a safe place can be created by taking an ASB on the adjacent track to which the worksite is to be set up, LOW is not permitted’
This WPHLR was available and was consulted by the Protection Officer (PO), who considered the WPHLR as a guide only. The protection plan was put to the Network Controller and was accepted, confirming the PO’s thoughts on the WPHLR.
Warning lights
In the network rule NSG 604 Indicators and signs, warning lights are described as;
Illuminated white or orange warning lights are provided at locations where workers on track have a restricted view of approaching rail traffic. If rail traffic approaches, the lights go out.
These lights can provide a warning to workers of approaching rail traffic. On detection of approaching rail traffic, the warning lights extinguish. This is intended to provide a fail-safe operation such that, if the light fails, or is observed to be extinguished, it must be assumed that a train is approaching.
The warning lights used by the Down lookout were illuminated white with a configuration of the example warning light in Figure 5.
Although the work itself was considered routine, the worksite area was mobile; that is, it was progressing along the rail corridor/tracks in the danger zone. The constantly changing terrain required the workers to be on both Up and Down tracks simultaneously and on multiple occasions. Both Up and Down lookouts were equipped with the same audible devices (horn and whistle) to warn the work group. In some cases, as in this incident, the position of the work group changed, whilst the position of the lookouts remained static.
In this incident, there were occasions when the workers passed through locations where there was restricted sighting (due to structures) and/or an absence of a safe place. It was likely that the ability of the lookouts to maintain sighting distance and provide timely warnings over the entire worksite area was impacted by the mobility of the work group conducting their inspection tasks.
Network Rule NWT 310 requires POs to reassess safety measures if conditions such as visibility, or work locations change. Additionally, if worksites are established over a large area, minimum warning times (MWTs) must be continually reassessed.
While the nature of the task required the workgroup to move over a large area and potentially affect MWT for the workgroup, there was no evidence of the PO reassessing MWTs.
The PO and Down lookout took on their respective roles at short notice, as other staff to fulfil these roles were not available. The PO also acted as the worksite supervisor and accompanied the inspection worker in the danger zone. The PO was satisfied that these additional duties did not interfere with his primary duty as a PO.
When interviewed, the PO explained his understanding of LOW and safe places. He expressed that when LOW was implemented over multiple rail tracks, safe places were created on adjacent clear rail tracks when a train approached on the same rail track as the workers.
The PO’s understanding of a safe place is not consistent with the definition of a safe place as defined in the RailSafe Glossary which states a safe place to be;
‘A place where workers and equipment cannot be struck by rail traffic.’
When a worker is on a live rail track there is a possibility of the worker being struck by rail traffic. Although the PO had been in the rail industry for 24 years and had worked as a qualified PO for 16 years, his understanding of a safe place in the rail corridor was no longer consistent with the definition.
The two lookouts and the inspection worker all agreed to the worksite protection plan and agreed with the PO on what constituted a safe place. It is likely the understanding of what constituted a safe place amongst all these workers increased the risk to the workers in the danger zone of being struck by rail traffic.
Responsibilities of the lookout
At Tempe, the Down lookout focused on acknowledging, by giving an ‘all clear’ hand signal and waiting for acknowledgement from an Up train. The Up train did not pose an immediate risk to the work group. The Down lookout focusing on acknowledging an Up train increased the risk to the work group of being struck by the Down train.
Where a lookout is required to remain vigilant for trains coming from a specific direction and provide adequate warning to people to get off the track, any distraction from this task increases the risk to the workgroup. NPR 711 stipulates that the lookout can only do this when workers and equipment are in a safe place, the ability for any lookout to perform this task effectively is questionable as the lookout must be able to establish the workgroup is clear of the track and will remain clear of the track before acknowledging the oncoming rail traffic.
There is limited time for a lookout to be satisfied of this when communication between the lookout and the workgroup is limited to non-verbal and visual communications. The act of acknowledging the oncoming train requires the lookout to face away from the workgroup and focus their attention on the oncoming train. The lookout cannot be sure members of the workgroup are clear and will remain clear when they turn away to acknowledge an oncoming train.
The Down lookout had the necessary competencies and experience to fulfil the role of a lookout. When interviewed, the Down lookout readily recalled the key responsibilities of that role and how they applied to the Tempe location. Notably, he explained that his decision to react to a train horn and provide an ‘all clear’ towards an Up train, was based on his interpretation and understanding of Network Rule NPR711 and from his practical experience. He reiterated that he reacted the same way to any train driver that sounded their train horn. This had been reinforced during his many years of track work experience, where he had personally received adverse reactions from drivers when they were not in receipt of an appropriate ‘all clear’ hand signal from lookouts.
Location of the Lookouts
The distance of the work group at 746 points from the Up lookout was approximately 350 metres. The distance of the work group from the Down lookout from 746 points was approximately 170 metres. At these locations the Down lookout was within sighting distance of the work group, however, the sighting distance to the Up lookout was obstructed by the overhead bridge stanchions.
The location and distance of the Up lookout from the work group would have made it difficult for the work group to hear the audible warning devices during their first two point inspections of 746 points and 748 points (see Figure 4).
Other ambient noise in closer proximity to the work group may have masked the sound of the horn and/or whistle which were the agreed audible devices used by the lookouts. Additionally, the overhead bridge between the Up lookout and the workgroup may have buffered the sound of the horn and whistle, making it harder for the work group to hear the audible warning. It is likely the audible warning devices would have been heard from the Down lookout.
The Down lookout was on the Up side of the work group during the inspections of 746 and 748 points. It is possible the Down lookout’s audible alarm coming from the Up side of the work group could have confused workers and delayed their evacuation from the danger zone. In most cases, Lookouts are on the extremities of the workgroup, so audible warnings from a lookout generally come from the direction the train is coming from.
Had the WPHLR been a document that required strict adherence, then the Network Controller should have informed the PO and an alternate protection method would have been sought.
Reference and adherence to the WPHLR is not apparent in the Network Rules and Procedures. Having a reference such as this is useful, but only if relevant people are aware of and are required to use it when planning work site protection.
Use of warning lights
From the approaches to the worksite at Tempe, there are a number of obstructions affecting visibility of the workers from an approaching train. From the down direction, these include an overbridge, stanchions and track curvature towards the Sydney end. Due to the restricted sighting on these track approaches, two illuminated white warning lights were provided for the Down Illawarra and Down Illawarra Local lines near Tempe to assist lookouts.
This warning light system, which relied on a lookout maintaining active observation, was utilised by the Down lookout as the Protection Officer considered the risk associated with using LOW had been successfully mitigated by using the warning lights. The warning lights are not designed with backup mechanisms (such as audible alarms, additional lights) to alert persons in the vicinity that the light/s in fact had extinguished and warned of an approaching train. However, while the purpose of warning lights is included in the Network Rules (NSG 604), they do not stipulate their application to specific worksite protection methods, like LOW. The warning lights at this location were not shown on older diagrams/network maps, worksite protection planning diagrams (WPPDs)[8], or Drivers Route Knowledge Diagrams (DRKDs).[9] The PO used DRKDs when implementing LOW.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
The incident involving train 59-J occurred during lookout working, when the Down lookout faced an approaching Up train to provide an ‘all clear’ hand signal to the train driver. At this time the Down lookout missed the change in aspect of the warning light indicating the approach of train service 59-J and could not provide adequate warning to the work group.
The Workgroup’s understanding and establishment of a safe place increased their risk of being struck by rail traffic.
The Down lookout’s interpretation and understanding of NPR711 contributed to his acknowledgment of the Up train.
The location and distance of the Up lookout from the work group may have made it difficult for the work group to hear the audible warning devices during their first two point inspections of 746 points and 748 points.
The location of the Down lookout presented a possibility of work group members being confused and delayed in responding to an audible warning.
Lookout Working (LOW) was implemented in an area deemed unsuitable for LOW on the Sydney Trains Worksite Protection Hazardous Locations Register (WPHLR). This is likely due to the WPHLR not being clearly stated as a reference with specific requirements that must be adhered to. [Safety issue]
Warning lights were utilised at Tempe to overcome sighting hazards and justify the use of LOW. Warning lights rely on lookouts maintaining continuous observation and their use were not specifically referenced in the LOW Network Rules. [Safety issue].
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the rail industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: Warning lights were utilised at Tempe to overcome sighting hazards and justify the use of Lookout Working (LOW). Warning lights rely on lookouts maintaining continuous observation and their use were not specifically referenced in the LOW Network Rules.
Single source of information for Lookout Working prohibition
Safety issue description: Lookout Working (LOW) was implemented in an area deemed unsuitable for LOW on the Sydney Trains Worksite Protection Hazardous Locations Register (WPHLR). This is likely due to the WPHLR not being clearly stated as a reference with specific requirements that must be adhered to.
The ATSB has investigated several accidents that have occurred when maintenance work was being carried out on or near railway tracks. Conducting work on or near a railway track can be dangerous if safeworking rules and procedures have not been correctly implemented to protect the worksite. Trains cannot stop quickly and any breakdown in the communication or management of a worksite can leave workers extremely vulnerable to dangerous situations.
What can you do
Operational safe working on track requires a high level of preparation and organisation. Whenever there is work taking place on or near a track, coordination and communication are essential to ensure adequate worksite protection is implemented. Before authority is granted to occupy or work near a track, it is essential that all information is clearly communicated and verified between the Protection Officer and the Network Control Officer.
An adequate briefing about the work site and effective communications equipment must be made available to the track workers. For track workers, it is vital to ensure that all levels of worksite protection have been fully implemented before commencing work on or near the track.
Similarly, before worksite protection is removed, it is essential that the Protection Officer and the Network Control Officer ensure all plant and workers have ceased operating and are positioned clear of the track.
ATSB comment
Safe work on track across Australia
The ATSB has also produced a safety issue investigation report, Safe work on track across Australia: Analysis of incident data, 2009 – 2014 (RI-2014-011), that is available from the ATSB website. This safety issue investigation reviews available data from across Australia of incidents and accidents relating to work on track. It is designed to provide industry with insights into the protection arrangements that are failing, and the reasons why, across many occurrences so that safety action can be designed to reduce future safe work on track occurrences.
To minimise risk, rail transport operators must ensure systems for safe work on track encourage workers accessing the rail corridor to communicate sufficient information to validate their worksite location, the adequacy of the protections in place, and their positioning in relation to any approaching train movements.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 2 August 2017, a Gippsland Aeronautics GA-8 aircraft registered VH-MQI, was operated by Arnhem Land Community Airlines, as a charter passenger flight from Milingimbi, Northern Territory (NT) to Djamardi aeroplane landing area (ALA),[1] NT. There was a pilot and five passengers on board.
At about 1225 Central Standard Time (CST), the aircraft joined the downwind leg of the circuit for runway 10 at Djamardi. The pilot observed the windsock indicating a light north-easterly wind.
Recorded data captured the incident approach, along with three previous approaches, conducted by VH-MQI to runway 10 during earlier flights to Djamardi. The data shows that on the incident approach, the aircraft turned onto the base leg of the circuit earlier than these three previous approaches (Figure 1).
After turning onto the base leg, the pilot believed the aircraft was becoming high on the desired approach path and reduced power to return to the desired path. After turning onto the final leg of the circuit, the pilot stabilised the aircraft at the selected approach speed of 65 kt with a rate of descent of about 500 feet per minute.
Figure 1: Representation of recorded data showing the tracks of four approaches, including the incident approach, made by VH-MQI to runway 10 at Djamardi ALA. The downwind, base and final legs of the circuit for runway 10 are also shown.
Source: Operator, annotated by ATSB
At about 1227 as the aircraft approached the runway at a height of about 50 ft, the pilot observed the airspeed reduce to 62 kt and lowered the nose to accelerate the aircraft. The pilot did not recall increasing power. Recorded data shows that at this time, the descent rate increased to 846 feet per minute. The pilot detected the increasing descent rate and flared the aircraft more positively than normal, however he was unable to arrest the rate of descent. The aircraft touched down hard on the main landing gear. The cargo pod (Figure 2) struck the runway.
After the aircraft touched down hard, the aircraft bounced and became airborne. The pilot then increased power to attempt to stabilise the aircraft and continue the landing. The aircraft then touched down a second time, on the nose landing gear first, and again bounced. The pilot further increased power, stabilised the aircraft, and landed.
The pilot and passengers were not injured in the incident, the aircraft sustained minor damage.
Figure 2: VH-MQI showing the cargo pod fitted to the aircraft (left) and damage sustained during the incident (right).
Source: Operator, annotated by ATSB
Pilot comments
The pilot of the aircraft made the following comments:
In response to the reducing airspeed, instead of lowering the nose, power should have been increased.
Prior to landing, the approach did not feel out of control, or overly unusual. Only when the aircraft landed hard did he realise that it was an abnormal situation.
Operator report
The operator of the aircraft conducted an investigation in to the incident and provided the following observations:
The early base turn led to a steeper approach descent profile.
A change in wind direction from a north-easterly, to a northerly as the aircraft approached the runway, combined with mechanical turbulence caused by trees, increased the aircraft descent rate.
After the pilot detected the reducing approach speed, the technique used to accelerate the aircraft was incorrect. Engine power should have been immediately increased.
The cargo pod, both main landing gear legs and the fairings where the landing gear legs enter the fuselage were damaged (Figure 3). The right main landing gear leg was also cracked.
Figure 3: Damage to left main landing gear leg (left), and damage to the right main landing gear leg and fairing (right).
Source: Operator, annotated by ATSB
Safety analysis
Late in the final approach, the pilot detected the airspeed reduce below the desired speed. In response, the pilot lowered the nose of the aircraft. This led to a high descent rate which could not be arrested prior to the hard landing.
The hard landing damaged the cargo pod, the main undercarriage legs and fairings.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The incorrect response to the reducing airspeed led to a high descent rate with insufficient height to recover. This resulted in the hard landing and aircraft damage.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Aircraft operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:
Flight crew training
The pilot has received training in the correct technique to arrest a high rate of descent during approach and landing.
Guidance material
The operator’s guidance material for Djamardi ALA has been updated to include a note advising of possible turbulence due to the surrounding trees.
Safety message
This incident highlights the importance of maintaining the correct approach descent profile and speed, and ensuring that pilots respond correctly to any deviations from the desired profile.
On the final approach, when the airplane is flown at a slower than normal airspeed, the pilot’s judgment of the rate of sink (descent) and the height of round out is difficult.
Whenever a slow speed approach is noted, apply power to accelerate the airplane and increase the lift to reduce the sink rate and to prevent a stall. This is done while still at a high enough altitude to re-establish the correct approach airspeed and attitude. If too slow and too low, it is best to execute a go-around.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the 18 July 2017, Pilatus PC‑12, registered VH-FDJ departed Alice Springs, Northern Territory for Adelaide, South Australia, on a routine single-pilot aeromedical patient transfer flight. During the approach into Adelaide, the pilot noted that the aircraft’s autopilot system failed to intercept the localiser for the Adelaide runway 23 instrument landing system (ILS) approach.
Unaware of why the autopilot did not intercept the localiser, the pilot then became focussed on determining the cause of the autopilot tracking issue while attempting to re-establish the aircraft back on the ILS to continue the approach. The pilot reported this resulted in high workload that was further increased by the tracking information displayed on the aircraft’s course deviation indicator not reflecting the position information being communicated by ATC.
The pilot continued the approach and commenced further descent after observing that the aircraft was close to becoming established on the localiser and that the glideslope was becoming active. Soon after, ATC notified the pilot that the aircraft was below the minimum permitted altitude for the aircraft’s position and instructed the pilot to climb the aircraft to a safe altitude. The pilot then conducted another ILS approach and landed.
What the ATSB found
The unexpected failure of the autoflight system to intercept and track the localiser resulted in the aircraft deviating from the surveyed instrument approach path and significantly increased the pilot’s workload.
The pilot’s focus on resolving the aircraft's lateral tracking and perceived autoflight issues during the localiser intercept decreased his attention on managing the aircraft’s approach profile. That led to the aircraft descending off-track below the minimum safe altitude.
Detection of the off‑track descent and subsequent intervention by the air traffic controller restored safe operation.
What's been done as a result
Following this incident, the operator amended their descent, arrival, and approach procedures, and training and checking procedures to be more prescriptive. In addition, the operator introduced dual global positioning systems, with moving map and chart overlay displays into their legacy aircraft, to improve pilot situation awareness.
Safety message
Adequate approach preparation, and management of aircraft flight profile and automation is vital to ensure pilots maintain manageable workloads and positional awareness during an approach. Additionally, pilots should not hesitate to conduct a go-around or a missed approach should the functionality of the aircraft’s automation, or the validity of positional information, be in doubt.
The occurrence
On the 18 July 2017 a Pilatus PC12, registered VH-FDJ, departed Alice Springs, Northern Territory, for a routine single-pilot aeromedical patient transfer flight to Adelaide, South Australia. The departure from Alice Springs and subsequent en-route phase of the flight was reported by the pilot to have proceeded normally.
Recorded data indicated that the aircraft reached the pilot’s calculated descent point from a cruise altitude of FL 250,[1] at about 42 NM (78 km) to the north-west of Adelaide Airport.
Before descending, the pilot reported that he obtained the available weather for Adelaide Airport and prepared the aircraft’s autoflight system for the arrival. This included programming the standard arrival route (STAR)[2] and instrument landing system (ILS)[3] approach frequency. The pilot also reported reviewing the respective arrival and approach charts displayed on the electronic flight bag screen.
At about 1240 Central Standard Time,[4] the aircraft left FL 250 to commence the Salty 1 STAR (Figure 1) and subsequently the runway 23[5] ILS. The pilot reported that as he was unfamiliar with the Salty 1 STAR, he elected to utilise the aircraft’s autoflight system and the Garmin 430 avionics system for navigation and descent.
Figure 1: Extract from the Adelaide Standard Instrument Arrival
Source: Airservices Australia modified by the Australian Transport Safety Bureau
The pilot reported that, during the descent, he noted a higher-than-normal groundspeed due to the strong westerly tailwind, however this decreased as the approach progressed to lower altitudes. As the aircraft approached the GLOBE waypoint, the pilot crosschecked the aircraft’s profile using the global positioning system (GPS) unit’s calculated profile. Noting that the aircraft was slightly high at that position, the pilot increased the selected descent rate on the autoflight system.
Just after passing the ELIZA waypoint and prior to turning inbound to intercept the localiser at GULLY, the pilot changed the primary navigation source from GPS navigation mode to a heading mode. This autoflight mode change was required to enable the pilot to set the inbound course for the ILS, to facilitate an intercept of the localiser for the runway 23 ILS approach. The pilot then recalled changing the autoflight system back to navigation mode to continue navigation to the waypoint GULLY and armed the approach mode for the ILS intercept. The estimated time available to complete these tasks was less than two minutes.
The pilot reported that the aircraft overshot the required intercept at GULLY. In response, he manipulated the autoflight system by turning the aircraft in the control wheel steering mode in an attempt to re-capture the localiser. At about that time, air traffic control (ATC) advised the pilot that the aircraft had flown through the localiser, ATC issued altitude and heading instructions to assist with a re-intercept. The pilot reported that this required him to cancel the current autoflight selections, including approach mode, to enable a heading to be selected and flown. The workload at this time was reported by the pilot to have been high as he attempted to determine the functionality of the aircraft’s autoflight and navigation systems.
Soon after, ATC gave the pilot radar information that positioned the aircraft left of the localiser. A clearance to conduct the ILS approach was then communicated, with a further request for the pilot to confirm when he was established on the approach. The pilot recalled that at that time he was still trying to determine the issues with the autoflight system and why the course deviation indicator (CDI) was giving conflicting information, indicating the aircraft was slightly right of the localiser. There was no recorded communication from the pilot reporting that the aircraft was established on the approach.
While trying to re-establish the aircraft on the localiser, the pilot observed the glideslope becoming active. As he believed that the aircraft was close to intercepting the inbound track, the descent was continued.
Recorded information confirmed that a short time later, ATC issued an altitude alert to the pilot to check his altitude. This was followed with instructions to climb to a new cleared altitude, to maintain the required terrain clearance, and to fly a different heading in anticipation of conducting another ILS approach.
The pilot reported that he followed the ATC issued radar vectors back to the commencement of the runway 23 ILS approach, where an intercept of the localiser using the autoflight system was made. The second approach was flown without issue.
Pilot information
The pilot was appropriately qualified for the flight, holding a Commercial Pilot Licence (Aeroplane). He also held an instrument rating for both multi-engine and single-engine aeroplanes. The pilot’s logbook recorded a total aeronautical experience of about 6,250 hours.
The logbook indicated that the pilot had about 5,800 hours in command of single-engine aircraft, which included about 640 hours flying Pilatus PC12 (PC12) aircraft.
The pilot had reportedly used the Garmin 430 avionics system before and had previous experience flying the PC12 legacy aircraft (see the section titled Operations). The pilots training file noted the pilot appeared to have no difficulty using the Garmin 430.
The appropriate flight reviews and proficiency checks had been conducted and the pilot was deemed competent to conduct line flying operations by the operator on the 5 July 2017.
The pilot held a valid class 1 aviation medical certificate and reported that he was well-rested prior to the flight and was in good health.
Weather
The pilot reported experiencing a strong westerly tailwind of about 57 kt during the descent and that the approach was conducted in instrument meteorological conditions. However, he noted that as the aircraft descended, the wind decreased and cloud layers were observed.
During the time of the aircraft’s arrival, the trend forecast for Adelaide Airport indicated a cloud base of 1,800 ft with broken cloud at 6,200 ft and wind from 280° M at 19 kt. There were also expected periods of up to 30 minutes duration where the weather would deteriorate, with the wind at 270° M at 22 kt gusting to 38 kt and the visibility reducing to 3,000 m in showers of rain.
Operations
The operator conducted aeromedical services throughout most regions of South Australia and the Northern Territory. The Pilatus PC12 aircraft was the only aircraft type used by the operator. The operator had three variants of the PC12, namely the PC12/45, PC12/47 and PC12/47E. The older PC12/45 and PC12/47 (sometimes referred to as the ‘legacy’) had different avionics and operating characteristics to the newer PC12/47E (referred to as the ‘NG’).
The operator had a valid Air Operator’s Certificate that enabled the use of PC12 aircraft in the charter and aerial work categories, which included the conduct of ambulance functions. The operator also had approval to conduct training and proficiency checks in accordance with the Civil Aviation Safety Regulations 1998.
The operator’s PC12 flight training manual provided basic reference material that related to initial pilot training. The flight training manual included an outline of the training syllabus, checklists and some lesson plans to assist the instructor with training preparation. The flight training manual did not provide any guidance to pilots as to the procedures and operational considerations while flying the PC12.
The flying operations manual outlined the standard operating procedures (SOPs) for a descent and approach. It included that:
At an appropriate time, the pilot is to review the intended approach procedure, including where applicable:
a. instrument or visual approach,
b. airfield information from ERSA, Jeppesen or OPS28 Airfield Register,
c. If an instrument approach procedure is required:
- correct chart, aids and frequencies, - airfield elevation and MSA [minimum sector altitude], - initial approach altitude and entry procedure, - approach procedure, - visual procedure - restrictions, runway, aircraft configuration, and - missed approach procedure.
Checklists used by pilots during flight listed that an ‘approach review’ was to be completed before transition. It was reported by the operator that in the case of longer flights, such as Alice Springs to Adelaide, an approach review and flight instrument setup actions should be completed before commencing the descent.
There was no guidance for pilots as to the operator’s expected flight instrument settings for the arrival. However, the operations manual highlighted the importance of pre-arrival planning and flight instrument set-up during the approach/landing phase. It included procedures for the conduct of a non-precision approach (other than area navigation[6]), area navigation approach and precision approach. There was no guidance to pilots as to when an approach review/brief and flight instrument setup should occur.
The operators expected instrument setup for VH-FDJ (FDJ) differed from other PC12 aircraft in the operator’s fleet due to variation in FDJ’s avionics. The operations manual required that specific familiarisation training was required for pilots flying VH-FDJ due to the differences with all other aircraft in the fleet. The pilot had conducted in-flight training in FDJ prior to the incident.
It was reported by the operator that a pilot flying FDJ should ensure that the inbound course was set on the CDI prior to commencing the STAR. This would alleviate the requirement to change between navigation modes once the STAR had commenced. It would also reduce pilot workload during the descent and arrival.
Training
The operator conducted ground theory training, endorsements, and line training for pilots flying the PC12 variants. The PC12 fleet comprised nine of the newer (NG) type aircraft fitted with ‘glass cockpit’ avionics, and eight older (legacy) type aircraft, with different avionics and operating characteristics. Training provided pilots with familiarity of both types. The occurrence pilot had significant previous experience on the legacy PC12 so the major component of his in command under supervision (ICUS) training concentrated on the NG variant.
The operator’s flight training records identified that the pilot had successfully completed all components of the operators training syllabus. However, notes made during the training identified that the pilot had difficulty at times with profile management, and approach preparation. These issues were not apparent during the pilot’s final flight check for commencement of line operations.
The pilot completed about 96 hours of in-flight training before being approved to conduct line flying operations on the 5 July 2017. The training consisted of 28 training flights, which included 24 flights with the newer PC12 NG variant and four flights with the PC12 legacy aircraft.
Following this occurrence, the pilot completed six remedial flights, two of which were in legacy aircraft. Those flights identified that the pilot required additional training with approach preparation. This included conducting more thorough approach briefings and ensuring that the approach checks and setup were not left too late in order to avoid high workload situations. The pilot’s training notes also emphasised the importance of conducting a go-around if the approach became unstable. At the end of this training the pilot was re‑checked and resumed line flying operations.
Related occurrences
A database search identified a number of occurrences with aircraft descending below the minimum safe altitude. The occurrences have primarily involved aircraft on approach to land. They include situations where pilot(s) attention has been on other tasks during higher workload phases of flight, such as during the later stages of an instrument approach. The ATSB has published the following related safety investigation reports.
AO-2015-018:Flight path management and descent toward the lower limit of controlled airspace involving Airbus A320, VH-VND, on approach to Melbourne Airport, Victoria, on 11 February 2015
On 11 February 2015, an Airbus A320 aircraft, registered VH‑VND and operated by Tiger Airways, was conducting a scheduled passenger service from Hobart Airport, Tasmania to Melbourne Airport, Victoria.
At about 1750 Eastern Daylight-saving Time, about 9 NM (17 km) north of Melbourne Airport, and after the flight crew had been cleared by air traffic control to conduct a visual approach, the aircraft descended below the minimum safe altitude, though the aircraft remained in controlled airspace.
During the descent, both flight crew became preoccupied with other tasks inside the flight deck, which had the effect of increasing their workload and distracting them from monitoring the aircraft’s flight path and altitude. About two minutes after commencing descent on the visual approach, the flight crew levelled the aircraft after realising that it appeared to be low on profile. A safety alert issued by air traffic control soon followed and in response, the aircraft was climbed to intercept the recommended visual approach descent profile. The remainder of the flight was uneventful and the aircraft landed on runway 16 at Melbourne Airport.
AO-2016-012:Descent below segment minimum safe altitude during a non-precision instrument approach involving Airbus A320, PK-AXY, 17 km WSW Perth Airport, Western Australia on 19 February 2016
On the evening of 19 February 2016, an Airbus A320 aircraft, registered PK-AXY and operated by PT Indonesia AirAsia was on a scheduled passenger service from Denpasar, Indonesia to Perth, Australia. During cruise, the captain’s flight management and guidance computer (FMGC1) failed. Due to the failure, the flight crew elected to use the first officer’s duplicate systems. For the aircraft’s arrival in Perth there was moderate to severe turbulence forecast below 3,000 ft with reports of windshear. The crew commenced an ILS approach to runway 21.
During the approach, the flight crew made a number of flight mode changes and autopilot selections, normal for an ILS approach with all aircraft operating systems available. However, some of those flight modes and autopilot selections relied on data from the failed FMGC1 and the auto-thrust system commanded increased engine thrust. The crew did not expect this engine response and elected to conduct a go-around. With an increasing crosswind on runway 21, the crew accepted a change of runway, to conduct a non-precision instrument approach to runway 06.
With the time available, the first officer programmed the new approach into his FMGC and conducted the approach briefing. During this period, the captain hand flew the aircraft and manually controlled the thrust. During the approach to runway 06, the crew descended the aircraft earlier than normal, but believed that they were on the correct flight path profile.
While descending, both flight crew became concerned that they could not visually identify the runway, and focused their attention outside the aircraft. At about that time, the approach controller received a ‘below minimum safe altitude’ warning for the aircraft. The controller alerted the crew of their low altitude and instructed them to conduct a go-around. The crew then conducted another approach to runway 06 and landed.
A number of factors lead to the pilot not being fully prepared for the arrival and subsequent instrument landing system (ILS) approach to Adelaide Airport. Although the importance of early preparation and maintenance of an appropriate flight path profile was reinforced during the pilot’s line training, the impact of not fully configuring the aircraft’s instrumentation earlier in the approach was likely not recognised by the pilot. This, combined with the effect of a tailwind during the approach, reduced the available time for the pilot prepare for the localiser intercept.
While it could not be determined why the aircraft’s autoflight system did not capture and track the localiser, it was possible that a late setup of the inbound course and arming of the approach provided insufficient time for the autopilot to turn the aircraft. From the available evidence it was likely that the pilot had less than two minutes to setup the instrumentation, arm the approach and prepare for the intercept.
It is possible that during preparation for the approach, the pilot incorrectly set the reciprocal of the inbound course on the aircraft’s course deviation indicator (CDI), resulting in displayed tracking indications that were not in the command sense. That would account for the difference between the aircraft’s position, relative to the localiser, displayed to the pilot compared to that advised by air traffic control. That discrepancy created confusion over the aircraft’s actual position and, in combination with the unexpected overshoot of the localiser, significantly increased the pilot’s workload in managing the ILS approach.
The pilot became focussed on resolving the aircraft's lateral tracking and perceived autoflight issues during the localiser intercept. His recollection of being aware that the aircraft was descending but unaware of its specific altitude was consistent with decreased attention on managing the aircraft’s approach profile. That led to the aircraft descending off-track below the minimum safe altitude until identified and remedied by the positive actions of the controller.
Pilot workload
When the aircraft did not automatically intercept the localiser as expected the pilot’s workload started to increase.
Workload has been defined by Orlady & Orlady (1999) as ’reflecting the interaction between a specific individual and the demands imposed by a particular task. Workload represents the cost incurred by the human operator in achieving a particular level of performance’.
Each individual has a finite set of mental resources which allow them to process information and identify appropriate tasks. The set is a variable trait, and will vary with many factors including the experience, training, recency and familiarity with a situation, stress and fatigue. Harris (2011) stated ’High workload is associated with increased error rates (and hence an associated decrease in safety margins) as well as having the effect of reducing overall productivity and increasing occupational stress’.
When the workload gets too high for the available set of resources, an individual will start to task shed, initially systematically and eventually indiscriminately as the workload continues to increase. Green et al. (1996) identified, ‘as the demands of the task, or the workload, are increased, the standard of our performance is achieved. Any increase in workload after this point leads to an overall degradation in performance. At extremely high levels of workload (overload), important information may be missed due to the narrowing or focussing of attention onto only one aspect of the task.’
The United Kingdom Civil Aviation Authority publication CAP 737 (2016) states workload ‘is linked to almost all other areas within cognition and performance, particularly attention, vigilance, fatigue, skills, and multi-tasking.’
Approach and landing is a well-known period of high workload for pilots. In this occurrence, the following factors had the potential to increase the pilot’s workload:
an increased ground speed
limited recent experience with the autoflight system fitted to this aircraft type
the high intrinsic workload of single-pilot IFR flight
restrictions of the single-channel autoflight system in setting up the ILS instrumentation.
While the pilot had the correct intentions for the approach, once the error arose with the aircraft tracking, the pilot became unable to effectively monitor the approach while troubleshooting the situation. Following the intervention of air traffic control, the situation was resolved and the second approach was flown without issue.
Training
The pilot’s initial training with the operator appeared to address identified approach management issues by the time he was cleared to conduct line flying operations. Recognising that subsequent remedial training identified the need for closer study and briefing of instrument approaches, it is difficult to ascertain if more approach consolidation conducted prior to the incident would have prevented it.
Despite profile management and approach preparation being reinforced during the pilot’s training, the standard operating procedures outlined in the company operations manual did not give guidance to pilots as to when and how the aircraft was expected to be configured for the approach. Although an approach review was required, information pertaining to the expected cockpit and approach setup may have benefited the occurrence pilot. More generally, the absence of such guidance increases the likelihood of greater variation in how approaches are conducted.
Safety issues and actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Royal Flying Doctor Service Central Operations
Since this occurrence, the operator has implemented the following improvements:
amended the descent, arrival and approach procedures to include more prescriptive requirements
upgraded the legacy fleet to include dual global positioning system equipment with moving map and chart overlay displays to improve pilot situation awareness
rewritten the Training and Checking manual to include more prescriptive training
strengthened the Safety Management System, including the introduction of a phased implementation of a change management program
changed the initial pilot training, which is now conducted by their recently approved Part 141 organisation.
Findings
From the evidence available, the following findings are made with respect to flight below the minimum permitted altitude involving Pilatus PC-12, registered VH-FDJ, that occurred about 19 km north‑east of Adelaide Airport, South Australia on 18 July 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Contributing factors
The unexpected failure of the autoflight system to intercept and track the localiser resulted in the aircraft deviating from the surveyed instrument approach path and significantly increased the pilot’s workload.
The pilot’s focus on resolving the aircraft's lateral tracking and perceived autoflight issues during the localiser intercept decreased his attention on managing the aircraft’s approach profile. That led to the aircraft descending off-track below the minimum safe altitude.
Other factors that increased risk
The pilot did not initiate a missed approach despite being uncertain of the displayed navigation system information and aircraft position. This limited the opportunity for the pilot to resolve any perceived navigation issues at a safe altitude and in a more controlled environment.
Approach guidance in the operations manual did not include detail of the expected cockpit and approach setup preparation. That increased the risk that variation in the conduct of approaches may be introduced into operations.
Other findings
Detection and intervention by the air traffic controller following the off‑track descent below the minimum permitted altitude restored safe operation.
Sources and submissions
Sources of information
The sources of information during the investigation included:
Airservices Australia
Civil Aviation Safety Authority
FlightAware
the flight crew and operator.
References
Civil Aviation Authority, 2016, CAP737 – Flight-crew human factors handbook, Civil Aviation Authority, United Kingdom.
Green RG, Muir H, James M, Gradwell, D, Green RL (1996) Human Factors For Pilots, Second Edition, Ashgate, England.
Harris, D (2011) Human Performance on the Flight Deck, Ashgate, England.
Orlady H & Orlady LM (1999) Human Factors in Multi-Crew Flight Operations, Ashgate, England.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Airservices Australia, the flight crew, the operator and the Civil Aviation Safety Authority.
A submission was received from the operator. The submission was reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Occurrence summary
Investigation number
AO-2017-075
Occurrence date
18/07/2017
Location
19 km north-east of Adelaide Airport
State
South Australia
Report release date
18/12/2018
Report status
Final
Investigation level
Defined
Investigation type
Occurrence Investigation
Investigation status
Completed
Mode of transport
Aviation
Aviation occurrence category
Flight below minimum altitude
Occurrence class
Incident
Highest injury level
None
Aircraft details
Manufacturer
Pilatus Aircraft Ltd
Model
PC-12/47
Registration
VH-FDJ
Serial number
861
Aircraft operator
Royal Flying Doctor Service of Australia Central Operations
On 10 July 2017, at about 1445 Coordinated Universal Time (UTC), an amateur-built Arion Lightning light sport aircraft, registered N273DB, fitted with a Jabiru 3300 engine, was substantially damaged during a forced landing following a partial loss of engine power near New River, Arizona, United States. The pilot, the sole occupant, received minor injuries.
As the accident occurred in the United States, the National Transportation Safety Board (NTSB) was responsible for investigating this occurrence. As part of its investigation, the NTSB notified the Australian Transport Safety Bureau (ATSB) as the state of manufacture of the engine. In accordance with clause 5.18 of Annex 13 to the Convention on International Civil Aviation, the ATSB appointed an accredited representative to liaise with the NTSB and initiated an investigation under the Australian Transport Safety Investigation Act 2003.
The ATSB has concluded its support of this investigation. On 9 August 2019, the NTSB released the final investigation report into this occurrence and it is available at www.ntsb.gov.
Any enquiries regarding the investigation and report should, in the first instance, be directed to the NTSB.
Occurrence summary
Investigation number
AE-2017-076
Occurrence date
10/07/2017
Location
New River, Arizona (17 miles north of Deer Valley Airport ((KDVT)), US