On 2 April 2017, at about 1730 Eastern Standard Time (EST), a Virgin Australia ATR - Gie Avions De Transport Regional ATR72-212A aircraft, registered VH-FVL, departed Moranbah for Brisbane, Queensland on a scheduled passenger service. There were two flight crew, two cabin crew and 38 passengers on board the aircraft. The captain was the pilot flying (PF) and the first officer was the pilot monitoring (PM).[1] The flight also acted as line training for the first officer.
While in the cruise, air traffic control (ATC) cleared the aircraft for the LAVEG ONE standard arrival route for runway 19 at Brisbane Airport. Weather conditions were clear and at 5,700 ft the crew established visual contact with the runway. ATC then gave them radar vectors to intercept the final approach leg.
At around 2,500 ft on descent, the captain disconnected the autopilot and manually flew the aircraft. ATC instructed the crew to track to a 5 NM (9.3 km) final approach leg for runway 19 and cleared the aircraft to descend to 1,700 ft for a visual approach. At 2,300 ft, the captain directed the first officer to select flap 15 and to set 140 kt on the automatic flight control system. The first officer then confirmed that this had been completed. The landing gear was extended soon after.
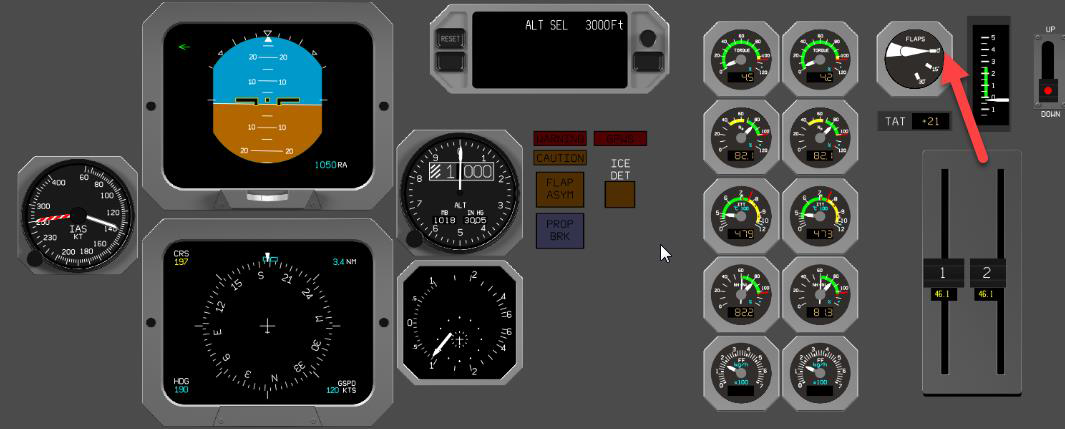
While the aircraft was turning onto the final approach leg, the captain directed the first officer to select flap 30, set the airspeed indicator bug to the approach speed (VAPP),[2] and start the before landing checklist. The first officer completed a radio call with ATC, moved the flap selection lever (Figure 1), set the approach speed (104 kt) and responded ‘V approach set’, and then started the checklist.
Figure 1: Location of flap lever on ATR72
Source: Virgin Australia
As the aircraft descended on the final approach leg, the crew noticed that the aircraft was not performing as expected. The captain had to keep adjusting the aircraft attitude and engine torque setting to control the speed. Passing about 1,000 ft, the captain recognised that the speed was too high, but thought that this could be corrected by 500 ft and continued the approach. The first officer also noticed the unusually high speed and called out ‘speed’ to alert the captain.
The flight crew had no recollection of completing the before landing checklist or completing the callout at 500 ft to ensure that aircraft was in a stabilised approach.[3] Passing 173 ft, the enhanced ground proximity warning system[4] (EGPWS) activated with the alert, TOO LOW FLAP. The captain immediately conducted a missed approach. During the subsequent climb, the captain called ‘flap 15, check power’ and the first officer responded accordingly.
When the aircraft achieved a positive rate of climb, the captain called ‘positive rate, gear up’. ATC cleared the aircraft to climb and then vectored them for a right base leg to conduct the same approach to runway 19. At this time, the first officer commented to the captain a concern that they may have left the flap at 15. After landing, the captain decided to stand the crew down and not conduct the next two sectors.
Recorded data
The operator extracted the flight data from the aircraft’s quick access recorder. It was recorded that the aircraft commenced the turn onto the final approach at 1,720 ft above the airport and was at 1,729 ft when the flaps lever was moved from 15 to 0 degrees at a calibrated air speed (CAS) of 139 kt.
At 900 ft, the air speed had increased to 148 kt and the aircraft was low on the approach. At 542 ft the aircraft had slowed to 123 kt, which coincided with the thrust lever angle set to idle.
Immediately after the TOO LOW FLAP warning at 173 ft, the thrust lever was moved to the go around position and the flap lever moved from flap 0 to flap 15.
The stall speed for the aircraft at flap 0 was about 106 kt at the estimated approach weight of 18 tonnes. The VAPP speed was set at 104 kt, which was below the flap 0 stall speed. The minimum speed recorded on approach was 114 kt at 507 ft.
The stick-shaker[5] activates at 15.9 degrees angle of attack[6] and the maximum angle of attack reached during the approach was 14.6 degrees.
Flap procedures
The operator’s ATR 72-500 standard operating procedures stated that all normal landings are conducted using flap 30. On approach, the pilot flying must call ‘flaps 30, set speed bug V approach’. The pilot monitoring is then required to check the speed, select flap 30, monitor the extension of the flap, and set the speed bug to VAPP and call ‘[speed] set’. The pilot flying then calls out the before landing checklist for the pilot monitoring to action. The last item on the before landing checklist is for both crew to check that flap 30 has been set.
The flap lever is in the 12 o’clock position for flap 0, in the 2 o’clock position for flap 15, and in the 5 o’clock position for flap 30. The flap position is also shown on the flap indicator where the needle points at 0, 15, or 30 (Figure 2).
Figure 2: A screen capture from the operator’s flight data showing the flap indicator positioned at 0 degrees while the aircraft was passing 1,000 feet on descent
Source: Operator, modified by the ATSB
Stabilised approach criteria
The operator’s stabilised approach criteria included that all approaches shall be stabilised by 1,000 ft above ground elevation. However, in terms of speed, if the pilot-in-command is confident the speed target will be achieved by no later than 500 ft above field elevation, the approach can continue.
The speed criteria is that the aircraft must be within -5 to +10 kt of the speed target.
If the speed remains outside the stabilised criteria at 500 ft above field elevation, or if at any time before it becomes apparent the stabilised criteria will not be met, then a go around must be initiated.
The VAPP set for flaps 30 on the day was 104 knots. At 507 ft, the airspeed was 114 kts, which was within the stabilised approach criteria. However, at 358 ft, the airspeed had increased to 128 kts.
The go around was initiated at 173 ft at an airspeed of 121 kts.
Captain’s comments
The captain provided the following comments:
The captain recalled seeing the first officer’s hand reaching out and grasping the flap lever when instructed to set flap 30, but was also busy hand flying the aircraft at the time.
While the aircraft is climbing on a go around, it is the pilot monitoring’s responsibility to call ‘positive rate’, but there was no call from the first officer so the captain made the call.
When they recognised that the aircraft was performing unusually, the captain thought it was an issue with the aircraft power settings because the aircraft was descending below the approach path.
Normally, both the pilot flying and pilot monitoring would check the flap settings when it is called in the checklist by checking the position of the flap lever, then the flap indicator, and say ‘set’. However, because the captain was busy controlling the aircraft, they may not have checked.
The first time the captain became aware that the flap was set to 0 degrees was during a review of the flight data animation produced by the operator.
The captain completed a fatigue report after the flight, although later reported not feeling overly tired during the flight. The captain had arrived at the airport to sign on at 1140 instead of 1340, due to confusion around the rostered flight time. However, to be safe the captain decided that the crew would not continue onto the next destination.
There are inherent risks with visual approaches at night, given that they are not using the instrument landing system.[7]
First officer’s comments
The first officer provided the following comments:
The workload of the crew increased during the approach when there was a combination of turning onto the final approach path, conducting a visual approach, managing radio calls with ATC and responding to the unexpected aircraft performance.
Flap settings are generally confirmed through the completion of the before landing checklist, whereby the flap lever and indicator must be visually checked. However, in this case, this part of the checklist happened during a high workload period, and it was subsequently rushed. This checklist item may have been missed.
The first officer recalled looking at the flap indicator and seeing movement, but may have wrongly assumed that the flaps were moving to flap 30 in lieu of flap 0.
Previous occurrences
A search of the ATSB’s database found the following occurrences where the incorrect flap setting was selected on approach:
On 28 July 2011, the crew of an Airbus A320 was on approach to Melbourne, Victoria (ATSB investigation AO-2011-089).[8] The approach brief included the requirement for flap 2[9] to be selected. At about 245 ft, the captain realised the landing checklist had not been completed and the crew received an EGPWS warning TOO LOW FLAP. The captain identified the aircraft was not in the landing configuration, including flaps and called for a go-around.
On 24 July 2013, the crew of an Airbus A320 was on approach to Newman Airport, Western Australia (ATSB investigation AO-2013-149).[10] Shortly after passing 500 ft above ground level, the crew received an EGPWS warning TOO LOW FLAP. Full flap was selected at about 185 ft and the aircraft landed shortly after.
On 2 April 2017, the crew of a Boeing 737 were on approach to land on runway 19 at Brisbane Airport (ATSB occurrence 201701579). At 1,400 ft the call for flap 30 was made, but flap 25 was selected. The landing checklist was commenced at 1,200 ft but interrupted by the issue of a landing clearance from air traffic control. The checklist was recommenced and completed at 1,000 ft, however, the flap setting was not identified. At 300 ft, the EGPWS warning TOO LOW FLAP activated and the crew conducted a missed approach.
Safety analysis
The approach and landing is known to be a phase of flight with a high workload due to the number of tasks to be completed in addition to monitoring the flight path. During the approach, as the aircraft was turning, the first officer was responding to a radio call and completing a checklist. It is likely that the first officer inadvertently selected the flap lever up from 15 to 0, instead of down to 30, and did not crosscheck the flap indicator before moving on to the other tasks. This inadvertent action led to an increase in the aircraft’s airspeed, which the flight crew recognised, but at the time were unable to ascertain why. The incorrect flap setting was not detected and a go around initiated after a ground proximity warning alerted the crew to an incorrect configuration at 173 ft.
Due to the high workload in managing the aircraft’s performance on approach, the crew did not detect the aircraft’s speed was exceeding the stabilised approach criteria of VAPP + 10 kts or that the aircraft was incorrectly configured with flap 0. Although at 507 ft, the airspeed was 114 kts, which was within the stabilised approach criteria with the VAPP set at 104 kts, at 358 ft, the airspeed had increased to 128 kts, which was outside the stabilised approach criteria.
Since the incorrect flap setting was not detected by the crew on approach, had they managed to slow the aircraft to the VAPP of 104 kts for flap 30, they would have been 2 kts below the stall speed for the actual flap setting (106 kts).
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
During the approach, the first officer moved the flap lever up from flap 15 to flap 0, instead of from flap 15 to flap 30 as intended. This resulted in an unstable approach.
The crew did not identify the incorrect flap setting until the ground proximity warning system alerted them to an incorrect configuration, likely due to workload.
Safety message
Approach and landing have a higher workload compared to other phases of flight because of the continuous monitoring of aircraft parameters and the external environment to maintain a stable approach. This investigation highlights the potential impact crew workload has on flight operations as it can lead to adding, shedding, or rescheduling actions. Handling approaches to land continues to be a safety priority for the ATSB.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 1 April 2017, the pilot of a Cessna R182 aircraft, registered VH-JXX, conducted a private flight from Broken Hill to Bathurst, New South Wales, with one passenger on board.
The aircraft arrived overhead Bathurst Airport at about 1130 Eastern Daylight-saving Time (EDT) and the pilot elected to join the circuit on a left downwind for runway 35. The pilot reported that the approach was normal, and that they aimed to touch down slightly beyond the runway threshold.
Due to a crosswind of about 8 kt, the pilot recalled that the left main wheel touched down immediately before the right. The propeller then struck the runway and the nose landing gear collapsed. The aircraft skidded a short distance before coming to rest on the runway.
The aircraft sustained substantial damage and the pilot and passenger were uninjured (Figure 1).
Figure 1: VH-JXX showing damage to the propeller and nose landing gear
Source: Aircraft owner
Pilot comments
The pilot commented that the approach seemed normal, all indications were normal, and the landing did not feel particularly hard. The first time they were aware something was not normal was when the nose of the aircraft contacted the runway. They had lowered the landing gear on downwind and confirmed the green light indicated the gear was safely down and locked, and had also verified the main wheels were down by doing a visual check.
Post-accident inspection
An aircraft maintenance engineer inspected the aircraft after the accident. The nose landing gear had collapsed, and the gear doors were broken. The cowl flaps were damaged, the firewall was buckled and the area under the floor in the area near the pedals was bent. There was no evidence of any fault other than the damage sustained in the impact.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The aircraft probably landed in a nose-low attitude resulting in a propeller strike and damage to the nose landing gear.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the afternoon of 30 March 2017, the flight crew of a British Aerospace Jetstream 3206 aircraft, registered VH-OTE, prepared to conduct Pelican Airlines flight FP314 from Canberra Airport, Australian Capital Territory, to Newcastle Airport (Williamtown), New South Wales. The flight crew comprised the captain and the first officer.
All pre-flight checks, taxi and engine run-ups were normal, however the left engine single red line computer was unserviceable (see Single red line section below). This did not prevent the aircraft from operating the flight but meant that the flight crew had to set the power of the engine using the manufacturer’s documented torque tables.
At about 1545 Eastern Daylight-saving Time,[1] the aircraft departed from runway 17 at Canberra Airport. As the aircraft passed about 7,000 ft on climb, the flight crew observed that the right engine was producing about 40 per cent torque, while the left was producing about 65 per cent torque. Fuel flow to the right engine and exhaust gas temperature (EGT) were also slightly lower than the left. The captain tried to use the power lever to increase torque to the right engine but it did not respond to produce greater than 40 per cent.
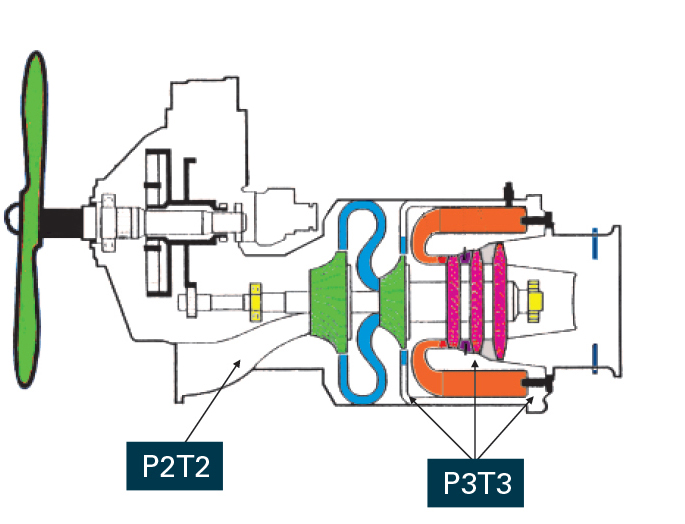
The first officer retrieved the appropriate section of the quick reference handbook (QRH), which they then actioned. The most common cause of low torque was icing on the compressor inlet pressure (P2T2) sensors (Figure 1). The QRH response was to turn on heat to melt the ice and wait 5 minutes to see if there was a power response.
After completing the actions and waiting the prescribed 5 minutes, there was still no positive response in the right engine to moving the power lever so the crew elected to return to Canberra Airport. At about 1559, passing about 9,000 ft, the first officer advised air traffic control (ATC) that they intended to return to Canberra and ATC provided a clearance for their approach.
About 5 minutes later, as the crew prepared for the approach to return, normal power returned to the right engine. Both engines were now responding to power lever inputs over the full range. Hence, the flight crew assessed that icing had been the cause of low torque and it had taken longer than 5 minutes for the ice to melt and the engine to respond.
At about 1604, when at about 9,000 ft, the first officer advised ATC that they had rectified the situation. The first officer advised that they intended to continue to Newcastle, and subsequently obtained a clearance to reroute.
Less than 2 minutes after turning the aircraft to track towards Newcastle, the right engine issue recurred. The captain verified that they could not get more than 40 per cent torque but that by pulling the power lever back, they could get flight idle torque. In those circumstances, the flight crew elected to return to Canberra but not to shut down the right engine.
The flight crew did not declare an emergency,[2] conducted a normal approach and, at about 1621, the aircraft landed on runway 17 at Canberra Airport without further incident.
Analysis
Flight crew assessment of issue
The aircraft was approaching freezing levels, with the outside temperature about 5 °C at the time the right engine torque decreased. The aircraft was not in visible moisture but there were showers in the area. The captain thought at the time that due to the venturi effect (lowering the temperature of the air flowing into the engine inlets), it could have been the start of freezing conditions for the engine and that they would have been turning on the anti-icing before long. The captain assessed that it was therefore possible that the P2T2 (and P3T3) inlets had frozen over and caused the reduction in available power.
Once the flight crew had turned the anti-icing system on (in accordance with the QRH checklist), they left it on. Therefore, when the problem recurred, they concluded that icing was not the cause.
Decision to return
The crew assessed that the engine was producing enough torque to operate the aircraft safely. As holding fuel was required in Newcastle and the cloud base was down to the minima specified for the approach, however, they elected to return to Canberra. There were no handling issues with the aircraft, and no adverse yaw. The crew assessed that with 40 per cent torque on the right engine, they could probably still cruise at the planned altitude of FL 150. [3]
During the descent, in accordance with normal procedures, the flight crew reduced the torque on both engines to 40 per cent, then 20 per cent on final approach and 12 per cent for landing. As they were able to reduce power on the right engine, the approach was therefore conducted without any asymmetric thrust.
Single red line
The single red line (SRL) simplifies how the pilot sets the engine torque. The SRL computer calculates the temperature difference between the turbine inlet temperature and exhaust gas temperature based on variables including pressure, altitude and true airspeed.
Without the SRL functioning, the flight crew use the manufacturer’s torque tables to determine the required values and, importantly, to ensure maximum EGT is not exceeded. The flight crew also used trend monitoring data (available in the cockpit) to see the relative torque and maximum EGT for each engine.
During the occurrence flight, the flight crew of VH-OTE were monitoring the EGT closely. According to the captain, the SRLs in the J3206 aircraft malfunctioned quite frequently but were readily rectified by maintenance engineers.
Weather
The captain reported that although there were some showers in Canberra at the time, the weather was ‘not too bad’. In Newcastle, however, there were severe storms, strong rain and winds, and the visibility and cloud were down to the approach minima. There was up to 60 minutes of holding fuel required in Newcastle due to the weather.
Engineering report
After the incident, aircraft maintenance engineers conducted ground runs of the engine. The engineers found no defects with the anti-ice valve, and the torque signal conditioner was normal. The engineers increased the maximum fuel flow setting on the fuel control unit (FCU) by 10 kg per hour and subsequent ground runs were satisfactory.
The aircraft subsequently operated several sectors with both engines operating normally. Three days later, the aircraft underwent scheduled maintenance. The maintenance engineers found that the No. 2 (right) engine FCU P3 piston was leaking into the P2 section. The P3-P2 is a dry section of the FCU so that any leaks are air-to-air.
The FCU was sent to an engine overhaul facility in the United States for further inspection. The FCU had accumulated 2,504.87 hours since new and had run for 1,713.97 hours while installed on VH-OTE. The inspection found corrosion on the P3 piston sleeve, which was replaced, along with a new piston seal and ring as part of the standard overhaul process.
The P3 air pressure positions the fuel metering valve to ensure the correct fuel to flow ratio. The facility engineers advised that an unresponsive power lever was not a normal result of a P3 piston seal leakage. The most frequent fault reported for P3 piston seal leakage was high flight idle fuel flows, which did not occur in this case.
The facility engineers had previously advised the aircraft operator that the engine inlet P2T2 sensor was known to be a possible cause of a non-responsive power lever and lack of control of engine power. An inspection of the sensor was carried out but no defect was found.
The FCU and P2T2 sensor were replaced and the issue did not recur.
Engine manufacturer comments
Honeywell advised that leakage of the FCU P3 piston into the P2 section can result in the inability of the FCU to reach the max fuel schedule. The symptoms of this condition would be similar to icing of the P2 inlet due to the increased pressure within the P2 section.
Threat and error management
When the problem occurred, the captain asked the first officer to retrieve the QRH. The first officer then read the relevant section and together the flight crew completed the actions. When the problem was not resolved after the prescribed 5-minute period, the flight crew discussed their options. They assessed that the weather in Newcastle was unacceptable, particularly with the possibility of having to conduct a missed approach if they were unable to get the required visibility at the minima. Therefore, the flight crew decided to return to Canberra Airport.
The flight crew also discussed the possibility of having to conduct a go-around. They assessed that a go-around with 40 per cent torque on the right engine was possible, that they would have been able to manage the asymmetric thrust, and that they would have been able to remain visual in the Canberra circuit area. There was a greater likelihood of having to go around at Newcastle due to weather, which reaffirmed their decision to return to Canberra.
Previous incident
The ATSB investigated an in-flight engine shutdown involving Pelican Airlines British Aerospace Jetstream 32 aircraft, registered VH-OTQ, that occurred in December 2016 (AO-2016-171). Shortly after the aircraft reached its cruising altitude, the right engine EGT gauge indicated a higher temperature than normal. The power lever did not respond to pilot inputs.
In accordance with the QRH, the flight crew shut down the right engine and returned to Newcastle Airport, New South Wales, from where they had departed. The flight crew did not declare a PAN, but the controller initiated an alert phase[4] during the aircraft’s approach.
In that incident, the fuel control unit’s bearing cage was broken, with many small fragments found to be interfering with the unit’s operation. The bearing cage held the bearing balls and kept them separated from each other.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
During climb, the right engine was limited to a reduced torque value and the engine did not respond to the pilot’s power lever inputs to increase torque. Due to this reduced torque and poor weather conditions in Newcastle, the flight crew elected to return to Canberra.
The reduced engine torque was consistent with leakage of the fuel control unit P3 piston into the P2 section.
The flight crew used effective communication and threat and error management techniques in responding to the issue. Although making an urgency (PAN) broadcast would certainly have appropriately alerted air traffic control (ATC) to the situation, the flight crew did not consider a PAN broadcast was necessary in this case as they had advised ATC of the reduced engine torque, and because a normal approach was possible.
Safety message
This incident provides a good example of effective threat and error management techniques. The flight crew were faced with an abnormal situation and made the decision to turn back to Canberra in a collaborative way.
It is important to broadcast a PAN or MAYDAY call, as appropriate, when time permits to alert air traffic control to an emergency situation. In response, air traffic controllers will provide assistance such as a priority landing to allow an aircraft to land as soon as possible. Airservices Australia publications In-flight emergencies and What happens when I declare an emergency provide relevant information.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 29 March 2017, a Piper PA-31-350 aircraft (Figure 1), registered VH-JQS, was on a private visual flight rules flight from Moorabbin, Victoria (Vic.) to Barwon Heads/Geelong aeroplane landing area (Barwon Heads ALA),[1] Vic. The pilot was the only person on board.
At about 1015 Australian Eastern Daylight Time (AEDT), the aircraft was on approach to runway 36 at Barwon Heads ALA. The aircraft was configured with the landing gear extended and full flaps selected.
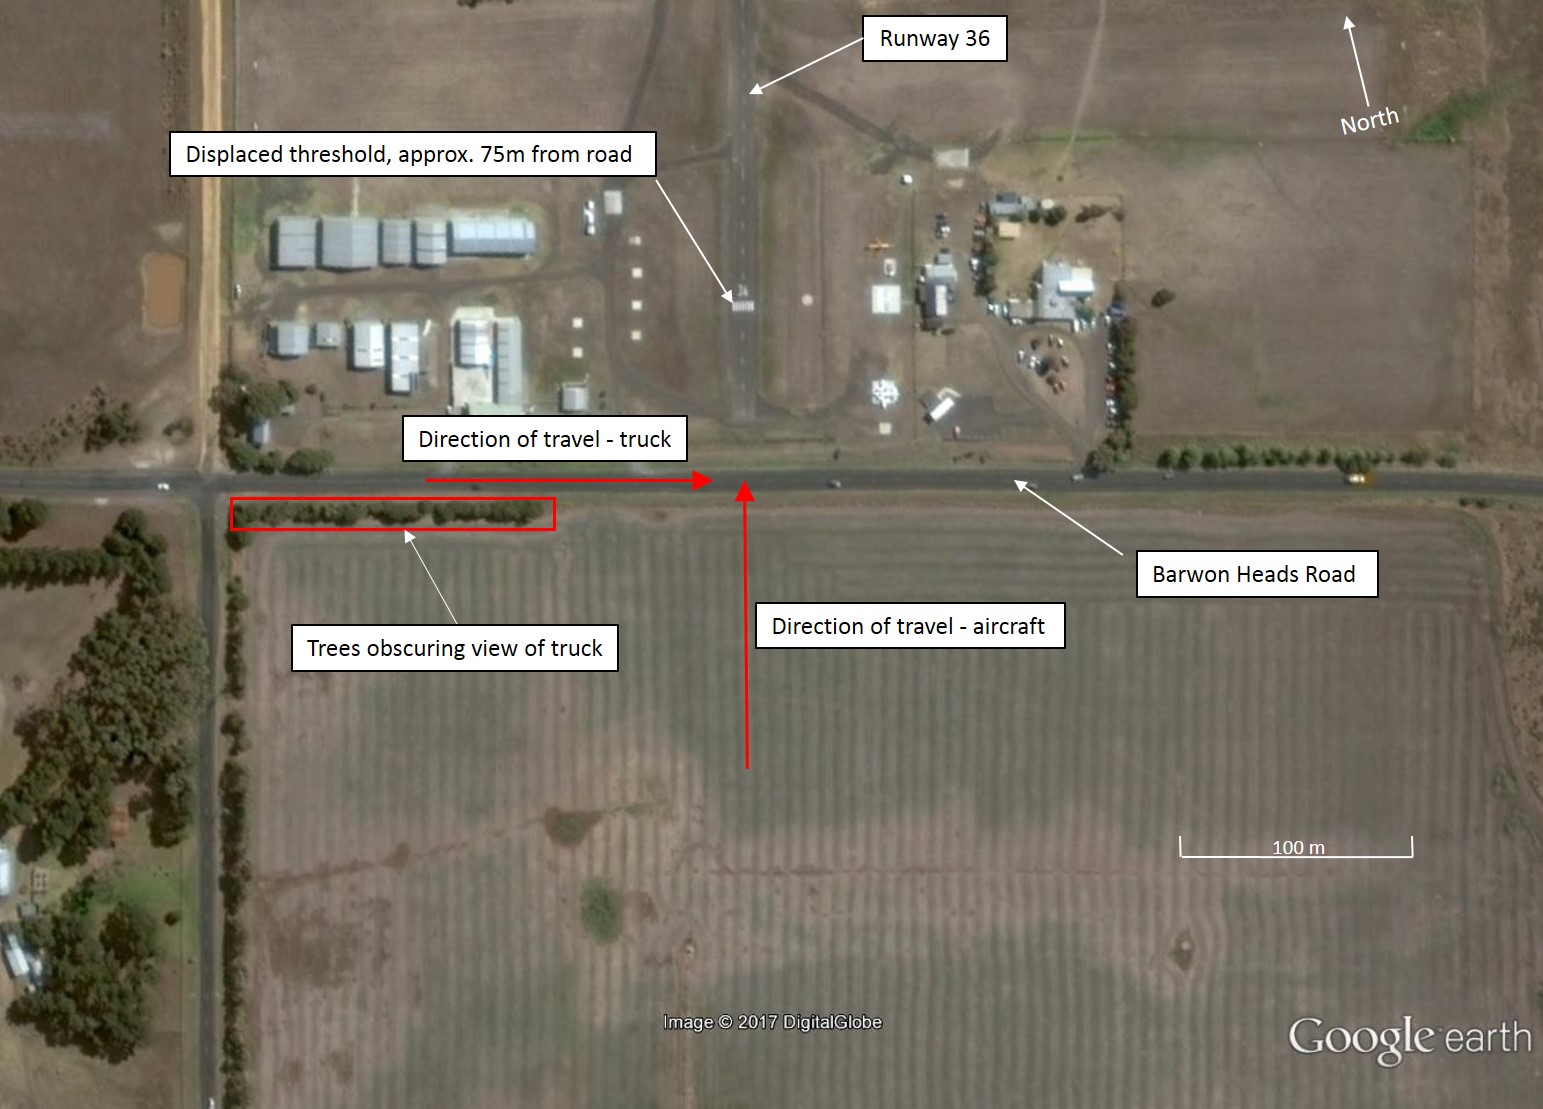
At a distance of about 0.5 NM (0.9 km) from runway 36, the pilot detected the aircraft becoming slightly low on the desired approach profile. The pilot retracted the flaps by 10° in an attempt to reduce the rate of descent. As the aircraft approached runway 36, the pilot noticed the aircraft was still lower than intended and decided to increase power. The pilot looked down momentarily at the throttle quadrant as they put their hand on the throttle control. As they looked back up, they observed a truck approaching from the left along Barwon Heads Road (Figure 2).
The pilot applied full power to conduct a go-around.[2] As full power was applied, the aircraft passed over Barwon Heads Road and the left main landing gear impacted the truck. The pilot observed the truck continue on Barwon Heads Road without stopping and the pilot continued with the go-around. The pilot elected to leave the landing gear extended in case it had sustained damage.
Figure 2: Barwon Heads/Geelong aeroplane landing area (ALA).
Source: Google Earth, annotated by ATSB
After completing the go-around, the pilot conducted two low passes over the airfield to determine the extent of any damage. During the first pass, the pilot contacted another pilot on the ground who had recently landed. The pilot on the ground was able to confirm that all three landing gear appeared to be intact. On the second pass, the pilot yawed[3] the aircraft left and right to ensure the landing gear was secure.
The pilot subsequently landed the aircraft without incident. The pilot was uninjured, and the aircraft sustained minor damage (Figure 3).
Figure 3: Damage to left main landing gear of VH-JQS.
Source: Pilot
Pilot comments
The pilot of VH-JQS provided the following comments:
They had flown into Barwon Heads regularly over the previous five to six years and were familiar with the airport, including the displaced threshold and the vicinity of the Barwon Heads Road.
In addition to flying duties, the pilot was also working as the company maintenance controller, and had recently taken on extra administrative duties. They stated that they were distracted during the incident flight by these additional pressures.
The desired approach profile was about a 3° (5 %) descent profile. The pilot was aiming to land about a quarter of the way into the runway in order to ensure clearance over Barwon Heads Road.
There were no issues with visibility or cloud cover but there was a gusting wind from the north-west. The aircraft became low on approach due to turbulence and windshear.
When they realised they were becoming low on the approach the pilot reduced flaps by 10° rather than apply power. This was done to avoid reheating the turbo chargers as they had already cooled.
The truck was not detected earlier as it had been obscured by a row of trees to the south-west of the airport.
Truck driver comments
The driver of the truck provided the following comments:
The truck driver felt what they thought was downwash from the aircraft but was unaware that contact had been made. At no time did they see the aircraft. It was only when the truck driver reached their destination that they saw the impact marks and damage to the top of the truck and realised contact had been made.
The truck was 3.950 m in height.
Airport operator comments
The airport operator provided the following comments:
In late 2014, Barwon Heads ALA underwent a number of upgrades. These upgrades included sealing of runway 36 and improvements to the runway lighting. As part of these upgrades, the airport operator also proposed lengthening runway 36 to the north so that the displaced threshold could be moved further north. This would have allowed more clearance for aircraft flying over Barwon Heads Road. The operator stated that this aspect of the application was rejected by the local council (see Local council comment below) so the application went ahead without this component.
The Aeronautical Information Package (AIP) En Route Supplement Australia (ERSA) states that prior permission is required to land at Barwon Heads ALA. This was done to convey information regarding the airport and runways. This information included the displaced threshold and road to the South of runway 36. The airport information was also available online (YBRS Runway Information - Barwon Heads Airport).
Local council comment
The local council commented that in general, the use of land as a transport hub (airport) is prohibited in a farming zone. However, the existing ALA site had operated as an airport for a period of almost 40 years and had existing use rights across the entire lot. These existing use rights, however, did not extend to the land north of the runway. Because of this, the council could not consider the part of the airport operator’s application relating to the extension of the runway to the north.
The use of power on the approach enables the rate of descent to be adjusted safely over a very wide range.
Additionally, the Civil Aviation Authority New Zealand circuit training guidance states that:
The approach path is monitored by reference to the correct runway perspective. Throughout the descent the aiming point, commonly the runway numbers or threshold, is monitored and the power adjusted as required to maintain a steady rate of descent to touchdown.
Power controls the rate of descent
With the aeroplane trimmed to maintain the required attitude (airspeed), if the aiming point moves up the windscreen, the aeroplane is undershooting – increase power. If the aim point moves down the windscreen, the aeroplane is overshooting – decrease power.
Both ends of a runway, not intended solely for agricultural operations, should have approach and take-off areas clear of objects above a 5 % slope for day and a 3.3 % slope for night operations.
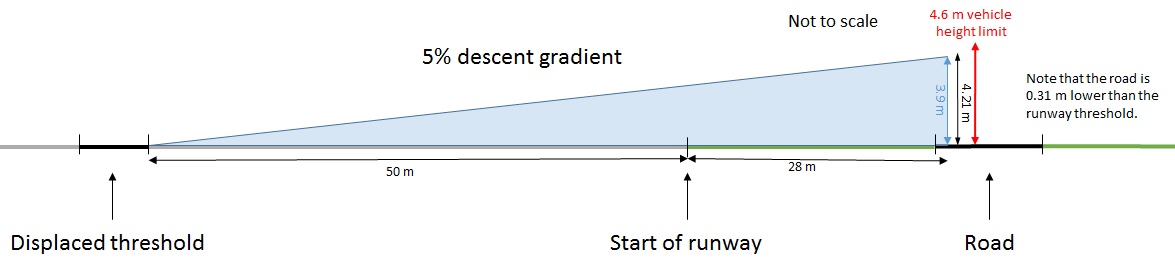
Barwon Heads Road is in close proximity to runway 36 (Figure 2). The start of runway 36 was about 25 m from the road, and the displaced threshold was 78 m from the road. Additionally, the elevation of the runway at the threshold was 0.31 m higher than that of the road. Using the 5 per cent approach recommended by CAAP 92-1, a distance of 78 m results in a height of 3.9 m (see Figure 5) over the runway elevation, providing a total road-crossing height of 4.21m. The VicRoads vehicle height limit in Victoria for road vehicles was 4.6 m.
Figure 5: Diagram showing a 5 per cent (3 degree) approach profile for Barwon Heads runway 36 and the proximity of Barwon Heads Road. A 5 per cent descent gradient aiming at the threshold results in aircraft passing over Barwon Heads Road at 4.21m which is lower than the VicRoads vehicle height limit of 4.6m.
Source: ATSB
While this incident occurred during daytime, runway 36 at Barwon Heads ALA is available for night use and is equipped with pilot activated lighting. Using the 3.3 per cent slope recommended by CAAP 92-1 for night operations, a distance of 78 m results in a height over Barwon Heads Road of 2.88 m (including the 0.31 m elevation difference). A review of the ATSB’s aviation occurrence database showed no similar occurrences on approach to runway 36 at Barwon Heads ALA have been reported to the ATSB.
Safety analysis
At about half a nautical mile from the runway, the aircraft became low on the approach. When the pilot recognised that the aircraft was too low, they elected to reduce the flap setting by 10° rather than add power. As the aircraft got closer to the runway, the aircraft was still lower than the desired approach profile, at which point the pilot elected to add power to gain height. Despite this action, the aircraft remained below the desired approach profile until it made contact with the truck.
The threshold of runway 36 was 78 m from Barwon Heads Road (Figure 2). Using the 5 per cent approach recommended by CAAP 92-1, a distance of 78 m results height of 3.9 m above the runway elevation. Combining this with the 0.31 m elevation difference, results in a clearance of 4.21 m which is less than the 4.6 m road vehicle height permitted in Victoria. Therefore, a normal approach aiming for the threshold of runway 36 at Barwon Heads can intersect with road vehicles on Barwon Heads Road.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The aircraft descended below the desired approach profile and the corrective action was not effective in sufficiently reducing the rate of descent.
The displaced threshold on runway 36 at Barwon Heads does not provide the level of clearance recommended by the Civil Aviation Safety Authority Civil Aviation Advisory Publication 92-1.
Safety message
The guidance provided by CAAP 92-1 regarding the recommended minimum physical characteristics of ALAs is not compulsory. Therefore, pilots should not expect the same conditions and protections at an ALA as they would expect at a registered airport. When preparing to operate to ALAs, pilots should gain as much local knowledge about the landing site as possible. This can be achieved by consulting the ERSA and calling ahead for prior permission and/or airfield information. Aerodrome operators can help facilitate this by distributing relevant information in the ERSA, on their website or by requesting prior permission, as done by Barwon Heads ALA.
This occurrence involved an experienced pilot with over 4,000 hours total flying time and over 1,000 hours as an instructor. Additionally, the pilot had flown into Barwon Heads ALA numerous times previously and was familiar with the displaced threshold and the proximity of the road. Despite this experience, and even with local knowledge, this occurrence resulted in the aircraft impacting a truck while on approach to Barwon Heads ALA. The ATSB’s aviation occurrence database shows that experience does not grant immunity from fatal accidents and in 2013 the ATSB published its sixth report of the avoidable accident series Experience won’t always save you.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
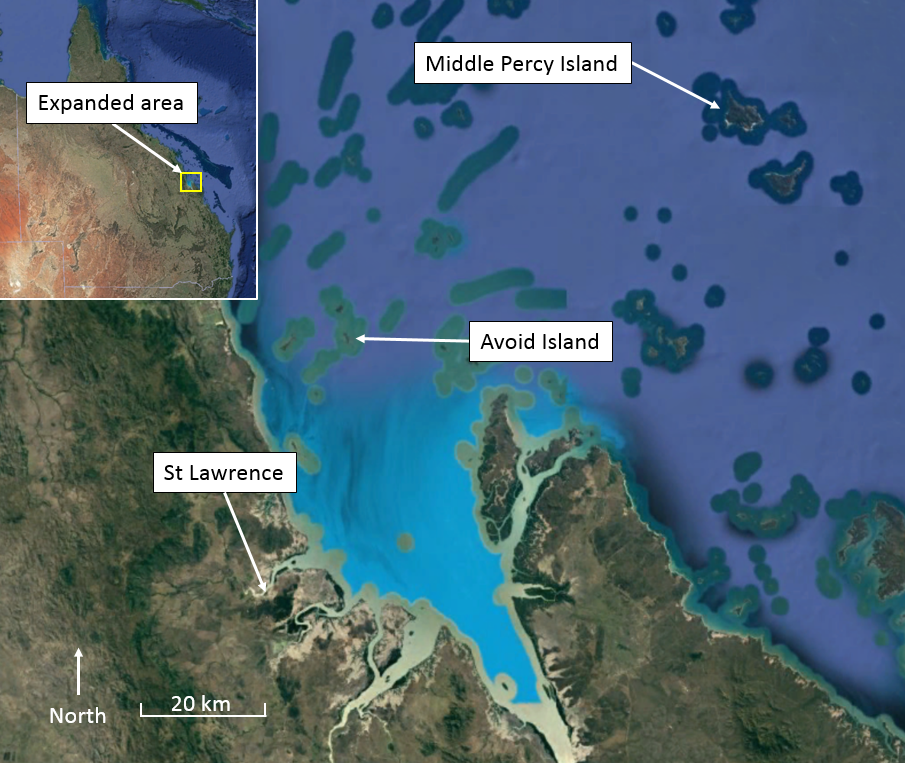
On the afternoon of 23 March 2017, the pilot of Gippsland Aeronautics GA-8 Airvan, VH-AZH, prepared for a departure from Avoid Island aeroplane landing area (ALA)[1] (Figure 1), Queensland (Qld) for a passenger charter flight to Mackay, Qld.
The company had elected to split the load of five passengers and cargo between two aircraft, a Cessna 206 and the GA-8.[2] On board the GA-8 were the pilot and three passengers, along with 30 kg of cargo and 92 kg of fuel, resulting in a take-off weight of 1,521 kg.[3]
While preparing for the departure, the pilot observed a 5–10 kt wind from the south-east and elected to use runway 14 for take-off. Runway 14 was a grass runway, 800 m long and included a slight rise in the middle. At the end of the runway was a vertical drop of about 2 meters down to a rocky beach.
Figure 1: Avoid Island ALA
Source: Google Earth, annotated by ATSB
At about 1555 Eastern Standard Time (EST), the pilot in the GA-8 commenced the take-off run ahead of the Cessna 206. During the take-off run, the pilot maintained slight back pressure on the control column to minimise the weight on the aircraft nose wheel. The rotation[4] speed for the take-off was 58 kt. The pilot elected to use a point about halfway along the runway as the decision point for the continuation of the take-off, this point was located just after the crest in the runway. As the aircraft passed the decision point, the pilot noted that the airspeed was about 40 knots and engine indications were normal. As the aircraft performance was satisfactory, the pilot elected to continue the take-off.
As the aircraft continued on the downhill side of the crest, the aircraft encountered a soft patch of runway surface, resulting in a slight deceleration. As performance quickly returned, the pilot did not consider this to be an issue.
As the aircraft approached the end of the runway, just prior to reaching the rotation speed, the pilot felt a significant deceleration. The pilot identified that insufficient runway remained to stop the aircraft, and in an attempt to avoid the aircraft falling over the vertical drop, elected to continue the take-off.
The aircraft did not take-off before overrunning the runway and became airborne as it passed over the vertical drop at a speed of about 50 kt. While manoeuvring to avoid large rocks and obstacles (Figure 2), the pilot maintained a nose high attitude to minimise the effect of any impact. The aircraft was unable to maintain height and descended over about a further 100 m until the landing gear and underside of the rear fuselage impacted rocks. As the aircraft decelerated, the impact through the rudder pedals forced the pilot’s ankle against the control column.
Figure 2: Accident site
Source: Operator, annotated by ATSB
After the aircraft came to rest, the passengers began to evacuate the aircraft. The pilot secured the aircraft and assisted the passengers with the evacuation. After securing the aircraft, the pilot then contacted the pilot of the Cessna 206 and advised them not to attempt to take-off.
The pilot of the Cessna 206 taxied that aircraft to the end of runway 14, contacted emergency services and provided assistance to the occupants of the GA-8.
The pilot of the GA-8 suffered a fractured ankle, the passengers were uninjured in the accident.
Pilot comments
The pilot of VH-AZH provided the following comments:
The pilot landed on runway 14 at Avoid Island ALA about 15 minutes prior to the accident flight. After landing, the pilot taxied the full length of the runway before turning around to return to the threshold of runway 14 to meet the passengers. While taxing, the pilot did not detect the soft patches in the runway. The pilot observed that the grass was dense and about 100 mm in length.
Performance calculation charts in the GA-8 pilot operating handbook did not provide for a runway with long wet grass and both an uphill and downhill component. Therefore, the pilot had used the ‘worst case’ scenario when calculating the take-off distance required[5] for runway 14 at Avoid Island ALA. The pilot calculated the take-off distance required to be 590 m when assuming a two percent upslope for the entire take-off run and short dry grass.
The wind conditions at the time of the take-off were not consistent. A change in wind speed or direction may have contributed to the accident.
The company chief pilot operated from Avoid Island ALA three days prior to the accident flight and found the ALA to be in good condition.
Operator comment
The operator of VH-AZH provided the following comments:
After the accident, the grass on the runway was mowed and the runway was inspected. The operator found the significant deceleration toward the end of the take-off run was the result of an area of soft runway surface and mud. During the pilot’s taxi after the previous landing, and during the accident take-off run, this area had been concealed by grass.
The pilot had received training at Avoid Island ALA and had recently operated to the ALA.
Weather and prior rainfall
The pilot reported 5–10 kt of wind from the south-east, cloud at about 1,500 ft and patches of drizzle in the Avoid Island area at the time of the accident.
Avoid Island did not have recorded weather observation data. Weather stations at nearby locations, Middle Percy Island and St Lawrence (Figure 3), reported the below rainfall totals[6] over the days prior to, and the day of the accident (23 March).
Table 1: Rainfall totals at Middle Percy Island and St Lawrence
Date
Middle Percy Island
St Lawrence
20 March
20.0 mm
16.2 mm
21 March
81.0 mm
70.8 mm
22 March
44.6 mm
66.4 mm
23 March
23.2 mm
36.4 mm
24 March
3.4 mm
46.2 mm
Total
172.2 mm
236.0 mm
Figure 3: Avoid Island location
Source: Google Earth, annotated by ATSB
Safety analysis
The Chief Pilot had visited the island three days prior to the accident flight and found the ALA in good condition, however, rainfall over the intervening period created soft patches in the runway surface.
The operator chose to split the load between two aircraft to provide more margin for the operation and the pilot calculated that sufficient runway was available for the GA-8 take-off. However, the soft patches, along with wet grass, prevented the aircraft from completing the take-off in the runway available.
Findings
The soft patches in the runway surface, concealed by grass, very likely degraded aircraft performance during take-off. The location of the soft patches towards the end of the runway prevented the aircraft taking off before the runway end.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Aircraft operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety action:
Aeroplane landing area management
The operator has taking over management of maintenance of the Avoid Island ALA. This will enable the operator to ensure that the ALA is suitable for proposed operations.
The operator is investigating the feasibility of works to improve drainage on the ALA.
The guidance documents for all regularly used ALAs have been updated and significantly expanded.
More rigorous pilot training of ALA operations will be conducted in future. The operator is investigating the use of an ALA which simulates the conditions of Avoid Island ALA and also has a cross runway to provide for crosswind training and assessment.
Safety message
When operating from an ALA, the pilot must take great care to ensure that the ALA condition is suitable for the proposed operation. ALA operations can present numerous and varied challenges which may affect the safety of flight. In this case, the Chief Pilot had visited the island just three days prior, however, rainfall over those three days had greatly impacted on the serviceability of the ALA. In addition, the dense grass present created difficulties in identifying the soft patches of runway.
The surface of a landing area should be assessed to determine its effect on aeroplane control and performance. For example, soft surfaces or the presence of long grass (over 150 mm) will increase take-off distances while moisture, loose gravel or any material that reduces braking effectiveness will increase landing distance.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 23 March 2017, at about 0942 Eastern Daylight-saving Time (EDT), a Regional Express SAAB 340B, registered VH-RXS (Figure 1), departed Dubbo Airport, New South Wales (NSW) to operate scheduled passenger flight ZL821 to Sydney, NSW. There were three crew and 23 passengers on board.
At about 0944, as the aircraft climbed through about 4,300 ft, the flight crew heard several bangs from the right engine accompanied by jolts through the aircraft. At the same time, the cockpit master warning illuminated and the right engine instruments displayed multiple warnings. These warnings were accompanied by a burning smell. The first officer, who was pilot flying,[1] identified a failure of the right engine and the flight crew immediately enacted the memory items of the engine failure checklist. The engine was shut down and the smell dissipated.
Figure 1: Regional Express SAAB 340B, registered VH-RXS
Source: VJ Bhana
After completing the memory items, the flight crew commenced the standard failure management procedures. The flight crew secured the right engine and established that the aircraft was performing satisfactorily. The flight crew declared a PAN[2] to air traffic control and requested emergency services. The flight crew then descended the aircraft to 4,000 ft and identified an area to the south-east of Dubbo which was clear of cloud and other traffic. The first officer manoeuvred the aircraft to this area in order to reduce workload while the flight crew continued the standard failure procedures. The captain identified Dubbo as the most suitable airport for landing. The flight crew reviewed the weather conditions for Dubbo and elected to conduct a visual approach and landing. The flight crew then briefed the cabin crew member on the situation, advised that they were returning to Dubbo and to expect a normal disembarkation. The captain then used the aircraft public address system to inform the passengers of the situation and that the aircraft was returning to Dubbo.
After briefing the passengers, the captain contacted the emergency services to ensure they were prepared for their arrival. In accordance with standard operating procedures, the captain took over the pilot flying role prior to landing.
At 1004 the aircraft landed on runway 05. No persons were injured, and the aircraft suffered minor damage in the incident.
Captain comments
The captain of the flight provided the following comments:
The first officer remained as the pilot flying until they were prepared to make the approach, as this allowed the captain to focus on the engine failure checklist.
Emergency procedures and simulator training undertaken by the flight crew was effective. The training prepared the flight crew well for the incident and along with the procedures in place, allowed the flight crew to effectively manage the engine failure.
During emergencies, it is important to follow procedures and not rush. This ensures all necessary actions are completed correctly. At each step, take a moment to review the overall situation and aircraft performance to ensure that it is safe to continue.
The engine failure checklist instructs the flight crew to consider a restart of the failed engine. At the time of the failure the right engine low oil pressure, over-temperature and chip detector[3] warnings all illuminated. As the warnings indicated that the engine was damaged and not recoverable, the captain elected not to attempt to restart it.
There was cloud in the area of the runway 05 area navigation (RNAV)[4] approach, the captain elected to remain clear of cloud and conduct a visual approach. As the runway 05 RNAV approach had quite a high minimum descent altitude, entering cloud may have resulted in a single engine missed approach.
After the flight, the captain received reports that passengers were concerned at the length of time taken after the engine failure for the flight crew to update them on the situation.
Engineering examination
The engine manufacturer conducted an engineering examination of the failed engine, however the examination was not completed in time for the release of this report.
An initial engineering examination found that the number four bearing failed. The bearing failure allowed the high-pressure compressor to move off-centreline within the engine. This caused further damage and led to complete failure of the engine.
The damage to the failed bearing was consistent with overheating due to a lack of lubrication. At the time of the release of this report, the reason for the lack of lubrication to the number four bearing had not been determined.
Safety analysis
The number four bearing within the right engine failed, possibly due to a lack of lubrication. As a result of the bearing failure, secondary damage occurred to the high-pressure compressor which led to a complete loss of power from the engine.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The right engine number four bearing failed, resulting in engine power loss.
Safety message
This incident highlights the importance of effective training and emergency procedures. Faced with an abnormal situation, the training provided to the flight crew ensured they were able to effectively implement the standard failure procedures, secure the failed engine and return for a safe landing.
During an emergency, flight crew prioritise the management of the emergency to ensure that the safety of the flight is not compromised. Completing the emergency procedures, along with the coordination of emergency services and communications with supporting agencies may absorb a significant amount of time before the flight crew are able to provide an update to passengers.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
During the period from 30 September 2016 to 3 November 2016, a series of unlawful communications occurred on multiple air traffic control (ATC) frequencies and the aircraft emergency frequency around the Melbourne area, Victoria.
On 30 September, the flight crew of an aircraft approaching Melbourne Airport, reported hearing two instructions on the Melbourne tower (Figure 1) ATC frequency. The Melbourne tower controller did not make or hear the instructions, and there was no impact on operations.
On 25 October, on three occasions, flight crew of aircraft landing on runway 34 at Melbourne Airport received instructions, via unlawful broadcasts from an individual impersonating a Melbourne tower controller, on the Melbourne tower frequency. The Melbourne tower controller heard the broadcasts and immediately provided clarifying instructions to the flight crew. There was no impact on aircraft operations.
Figure 1: Melbourne airport ATC tower
Source: Airservices Australia
On 27 October, at about 1429 eastern daylight time, ATC received reports from flight crew of emergency broadcasts on the aircraft emergency frequency, apparently being transmitted by multiple aircraft. The broadcasts indicated an inflight emergency to the north of Melbourne. In response to these reports, ATC declared a distress phase[1] and, in accordance with emergency procedures, contacted the Australian Maritime Safety Authority (AMSA). At 1502, AMSA confirmed that the broadcasts were false and cancelled the distress phase.
At 1539, ATC received two further reports of emergency broadcasts on the aircraft emergency frequency. The broadcasts used the registration of an aircraft which was operating to the north of Melbourne at that time. The broadcasts indicated an inflight emergency overhead the Melbourne metropolitan area. ATC immediately declared a distress phase. Air traffic control then contacted the aircraft, the flight crew confirmed that they had not made the broadcasts and that operations were normal. At 1542, having confirmed that the emergency broadcasts on the aircraft emergency frequency were false, ATC cancelled the distress phase.
At 1721, a Boeing 737-800 aircraft approached runway 16 at Melbourne airport. As the aircraft descended through about 200 ft above ground level, the flight crew received the instruction ‘go around’.[2] The flight crew could not determine a reason for the instruction, however, recognising that questioning the instruction at that time could create further confusion, elected to conduct the go around. As the flight crew commenced the go around, the controller confirmed that the instruction had not been broadcast by the controller and that the aircraft remained cleared to land. As the flight crew had already commenced the go around, they elected to continue the procedure. The aircraft returned to land without further incident.
At 1724, ATC personnel updated the Melbourne Airport automatic traffic information service (ATIS)[3] used by arriving and departing aircraft crew for airport information to include notification of the unlawful broadcasts.
At 1739, the ATIS was further updated to include the information that ATC would use light signals to confirm aircraft clearances in the event of further unlawful broadcasts.
At 1929, the Avalon approach controller received an emergency broadcast using the registration of an aircraft which was operating to the north-west of Melbourne at that time. Air traffic control contacted the aircraft, the flight crew confirmed that they had not made the broadcasts and that operations were normal. No distress phase was raised and there was no impact on operations.
On 31 October, ATC received a report from the flight crew of an aircraft departing Melbourne Airport of unlawful broadcasts on the aircraft emergency frequency. The broadcasts simulated aircraft ground proximity and warning system aural alarms. There was no impact on operations.
On 3 November, ATC received multiple reports from flight crew of unlawful broadcasts occurring on the aircraft emergency frequency. The broadcasts indicated an inflight emergency, the flight crew receiving the broadcast responded, however no reply was received. There was no impact on operations.
Air Traffic Control procedures
The provider of civil ATC services in Australia, Airservices Australia, had the following procedures in place to manage unlawful broadcasts on ATC frequencies:
Manual of air traffic services (MATS)
The Airservices Australia MATS contained the following procedure for managing malicious radio transmissions:
Report unauthorised (malicious) transmissions to aircraft as detailed in local instructions.
MATS also contained the following instructions to assist controllers in managing unforeseen situations which have not been documented:
Best judgement
Do not allow anything in these instructions to preclude you from exercising your best
judgement and initiative when:
a) the safety of an aircraft may be considered to be in doubt; or
b) a situation is not covered specifically by these instructions.
Local Instructions
Melbourne tower local instructions did not provide procedures or guidance to controllers on the handling of unlawful communications.
ATC personnel response
In the absence of detailed procedures, ATC personnel used the following to manage the impact of the unlawful communications:
Shift managers briefed controllers about the activity.
Shift managers also provided controllers with recordings of previous events to familiarise the controllers with the individual’s voice.
Controllers contacted individual aircraft directly to advise that unlawful broadcasts were occurring. When controllers heard unlawful broadcasts, they immediately clarified clearance details with the affected aircraft.
The no-radio procedure of using light signals to provide aircraft clearance details was determined to be a suitable method to confirm clearances.
Included a warning on the Melbourne Airport ATIS.
Recorded all available information.
Airservices Australia Comment
The provider of civil air traffic services within Australia, Airservices Australia, provided the following comments:
Airservices considers that the established organisational resilience/crisis management practices proved effective to handle each unlawful communication event. Given it is not possible to document all elements of scenarios that a controller may face, Airservices training and risk management practices are designed to enable controllers to manage a range of unusual situations which are not documented.
Controllers will always assume that an ATC broadcast is real, as was prevalent in these occurrences. The In-Flight Emergency Response checklist was utilised and followed until it was determined that the broadcasts were hoax calls and the aircraft were not in distress. Having an established procedure to manage hoax calls may lead to ambiguity with regards to the validity of a broadcast.
The development of detailed procedures may not achieve a safety outcome as it would be impracticable to cater for all situations. Furthermore, it may restrict initiative required by ATC to safely manage each scenario on a case-by-case basis.
Safety analysis
Despite an absence of local instructions, ATC personnel were able to use best judgement to implement effective methods to manage the unlawful communications.
The false emergencies scenarios were handled quickly and effectively within existing emergency procedures. Air traffic control and AMSA personnel were able to quickly confirm the non-existence of the emergency situations and cancel the distress phases.
The unlawful communications resulted in minimal impact on aircraft, ATC and AMSA operations.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation.
There were minimal documented local instructions in place for managing unlawful communications.
Despite an absence of documented local instructions, training and crisis management practices enabled ATC personnel to effectively manage the unlawful communications to minimise the impact on aircraft and AMSA operations.
ATSB comment
The unlawful communications were broadcast by one individual. The Australian Federal Police arrested and charged this individual with five offences relating to the communications.
Safety message
Unlawful communications transmitted with malicious intent, while rare, have the potential to impact the safe operation of aircraft and, as demonstrated by this series of events, divert AMSA away from their core tasks.
Despite an absence of local instructions, ATC personnel were able to use best judgement to implement effective methods to quickly and effectively manage the unlawful communications to minimise the risk to flight safety.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 23 November 2016, a Fairchild SA226TC, registered VH-SSV (SSV), departed from Brisbane Airport, Queensland, for a passenger charter flight to the Theodore aircraft landing area (ALA), Queensland. On board the aircraft were the pilot and five passengers.
When SSV arrived at Theodore, the aircraft joined the circuit on the downwind leg for runway 17 at 2,100 ft[1] using the area QNH.[2] The pilot turned the aircraft through the base leg of the circuit, using a constant radius turn, and rolled the aircraft to wings level for the final approach at about 1,400 ft.
In the early stages of the final approach, the pilot noticed the aircraft sink,[3] so they[4] increased power slightly to compensate and by mid final they were satisfied the aircraft was stable on the desired approach path profile. On short final, the pilot checked the airspeed and noted the aircraft was at their calculated airspeed of VREF[5] +2 (111 kt). Shortly after they checked the airspeed, the pilot noticed the aircraft sink, so they pulled back on the elevator control and started to increase power, but the main wheels touched down just prior to the runway threshold. A loud bang was heard within the aircraft and the pilot immediately suspected the aircraft had struck one of the runway 17 threshold solar powered lights.
The landing was completed and after parking the aircraft on the apron, a passenger reported to the pilot that the right wing was leaking fuel. On inspection, the pilot found a puncture to the underside of the right wing, just outboard from the right engine nacelle, which had breached the fuel tank (Figure 1). They concluded it was probably the result of debris from the damaged runway light flicked up by the right main wheel tyre. There were no injuries and the aircraft received minor damage.
Figure 1: Damage to the underside of wing
Source: Pilot
Landing threshold height
Theodore ALA is situated about 560 km north-west of Brisbane. The ALA has a sealed runway strip surface at an elevation of 560 ft and direction 170-350. The runway length is 1,342 m with a slight down slope to the south (runway 17) and is fitted with low intensity runway lights at the thresholds and at 90 m intervals alongside the runway strip. The pilot used the first row of runway lights from the threshold as their landing aim point.
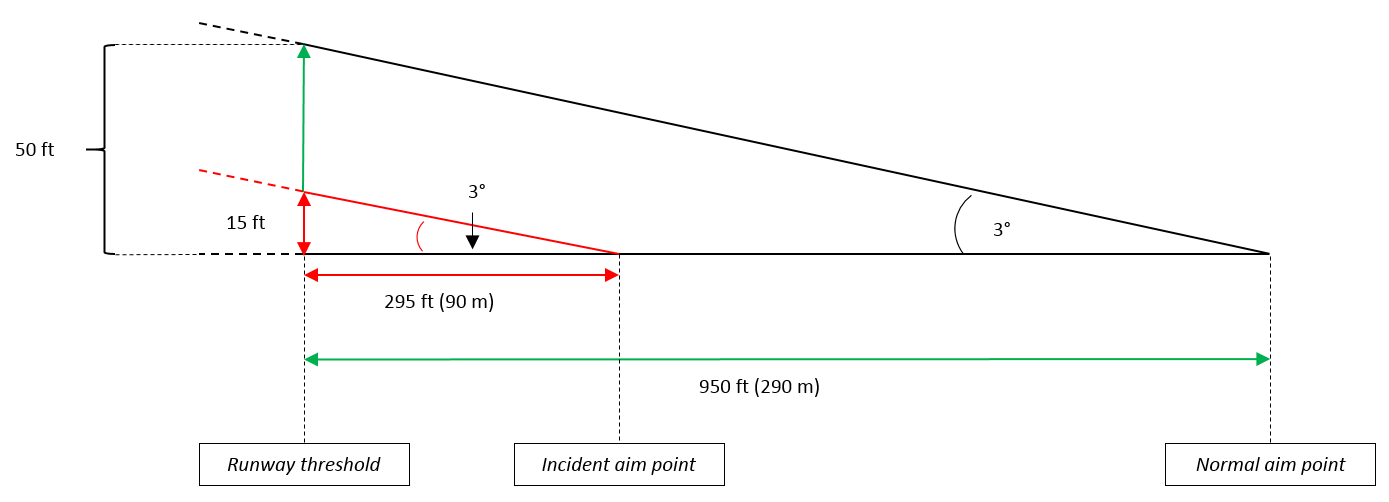
The landing distance required (LDR) begins at a height of 50 ft from over the runway threshold. The pilot reported flying a standard 3° approach path angle. However, a 3° approach path, with a threshold height of 50 ft is based on a landing aim point about 290 m from the runway threshold. Using the same approach path angle with an aim point 90 m from the runway threshold will reduce the threshold height to about 15 ft (Figure 2).
Figure 2: Runway threshold heights
Source: ATSB (not drawn to scale)
Landing distance performance calculations
Aeroplane flight manual
The pilot used the aeroplane flight manual (AFM) for their performance calculations. The AFM has six sections. The first four sections of the AFM were approved by the United States Federal Aviation Administration (state of manufacture). Section six was manufacturer’s data for calculating performance. The manufacturer’s data section provided two approach options for calculating LDR. One option was the short field landing approach at VREF 1.1 Vs0[6] with full reverse thrust on landing. The other option was the normal approach at VREF 1.3 Vs0 with no reverse thrust on landing.
The AFM charts are only applicable to level runways. Runway slope is not included as a factor in any of the landing distance charts.
Civil Aviation Order 20.7.4
Civil Aviation Order (CAO) 20.7.4 – Aeroplane weight and performance limitations – aeroplanes not above 5,700 kg – private, aerial work and charter operations – paragraph 10 was the CAO for defining how to calculate LDR. Paragraph 10.1 required the calculated LDR to be multiplied by a safety factor, which was 1.43 for SSV. However, paragraph 10.1 was subject to paragraph 10.3. Paragraph 10.3 stated:
Where there is an approved foreign flight manual or a manufacturer’s data manual for an aeroplane that sets out the landing distance required for that aeroplane, then that aeroplane must be operated so as to comply with the requirements set out in paragraphs 10.1 and 10.2 or the requirements relating to landing distance set out in either of those manuals.[7]
Therefore, CAO 20.7.4 did not require a multiplication factor to be applied if LDR was calculated from either the approved foreign flight manual[8] or manufacturer’s data manual.
Company operations manual
The company operations manual for the Fairchild SA226TC provided the following directions to their pilots for performance calculations:
The pilot-in-command is responsible for ensuring the aircraft is capable of the performance required for the operation. This assessment should include take-off and landing distances, climb performance, and single engine performance.
Charts supplied in the manufacturer’s approved flight manual for this aircraft are American charts and are not factored as required by CAO 20.7.4. Take-off and landing information derived from these charts must be factored to comply with the CAOs, specifically:
Take-off distances must be multiplied by a factor of 1.25
Landing distances must be multiplied by a factor of 1.43
While the operations manual referenced factoring as a regulatory requirement, it was also company policy to factor landing distances in accordance with CAO 20.7.4 paragraph 10.1, in order to include a safety margin to the flight manual charts, which were un-factored charts.
Pilot calculations
The pilot calculated a short field approach and normal approach LDR with the following results:
Short field approach VREF 93 kt. Un-factored LDR 590 m; factored LDR 840 m.
Normal approach VREF 109 kt. Un-factored LDR 1,080 m; factored LDR 1,543 m.
Therefore, for a runway length of 1,342 m, both approaches were suitable un-factored, but only the short field approach was suitable when factored. The calculations did not include a factor for runway slope, but the pilot was aware of a downslope on runway 17 from their previous experience.
Pilot’s minimum control speed experience in SA226TC
The pilot noted that the AFM-published VMC[9] for the aeroplane was 94 kt, which was greater than their calculated short field approach VREF, but less than their calculated normal approach VREF.
During the pilot’s SA226TC endorsement training in the simulator, the first time they were given an engine failure at V1 they were unable to arrest the yaw and roll in a timely manner and crashed the aircraft (simulator). The SA226TC does not have an auto-feathering[10] propeller mechanism fitted. It is fitted with a negative torque sensing system (NTS system). In the event of an engine failure during flight, the NTS system provides automatic drag reduction by moving the propeller blades towards the feather setting. Once the drag reduces and the negative torque decreases, the feather valve returns to its normal position under the influence of its spring, and the propeller blades move toward the fine (unfeathered) setting. This condition is repetitive until the pilot manually feathers the propeller and is called ‘NTSing.’
The pilot then successfully completed the simulator exercise three more times, completing all drills and feathering the propeller in an appropriate time frame. However, the minimum angle of bank they achieved while regaining control of the aircraft (simulator) was 30°.
From their simulator experiences of the asymmetric handling qualities of the aircraft near VMC, the pilot was uncomfortable conducting approaches at a calculated VREF below or close to VMC.
Approach profile and aim point selection
The pilot reported that they had flown to Theodore numerous times previously, which included 28 times during 2016 in SSV. They did not want to conduct an approach using a VREF less than VMC. Therefore, they employed the normal approach profile with a VREF 1.3 Vs0, with the LDR factored in accordance with their operations manual. This produced an LDR greater than landing distance available. In addition, the AFM charts assume a level surface. There is no factor for runway slope and downslope will increase LDR. To minimise the landing distance, the pilot applied full reverse thrust in addition to wheel braking after touchdown for the ground roll when landing at Theodore.
Runway aim point markers, located about 300 m from the threshold on sealed runways, were the standard aim point employed by the pilot. However, unsealed runways, such as Theodore, do not require aim point markers. Consequently, the pilot utilised the runway side lights for their aim point. The pilot understood that the landing distance available was between their calculated un-factored and factored LDR for a normal approach using VREF 1.3 Vs0, but the downslope on runway 17 would increase their landing distance. This led them to select the first row of runway lights as their aim point in order to maximise the runway distance available for braking. They estimated, from their previous experience, that the normal approach with the use of full reverse thrust on landing would result in a landing distance about 100 m longer than that calculated using a short field approach.
Stabilised approach criteria
The company had a ‘no-fault’ go-around policy and published stabilised approach criteria. For a visual approach the criteria apply from 300 ft above ground level. There were several criteria listed for a stabilised approach, which included:
The aircraft is on the desired flight path, e.g. established on final/base leg;
Only small pitch and heading changes are required to maintain the desired flight path;
For circling approaches, the wings must be level on final not below 300 ft above ground level; indicated airspeed at threshold (50 ft) within tolerance (VREF +5, -0).
During the approach, the aircraft was flown on the pilot’s desired flight path. On short final the pilot checked their airspeed, which was within the threshold stabilised approach criteria and continued the approach. When the aircraft began to sink on short final, the pilot pulled back on the elevator to pitch the aircraft nose upward and applied power in an attempt to avoid an early touchdown, but there was insufficient height to recover.
Convective weather
The pilot reported the incident occurred at about 1657 Eastern Standard Time (EST) and the temperature was about 36 °C. The runway surface is bitumen and the ALA is surrounded by paddocks. On the approach to runway 17, some of the paddocks had been ploughed in preparation for planting and some had light coloured crops. Following discussions between the pilot and their chief pilot, they concluded that because the wind speed in the area at the time was light, the sink may have been the result of local convective currents (known as thermals).
Convective currents are the result of uneven surface heating, which sets up areas of local circulation as the air flows from areas of higher pressure towards areas of lower pressure. Ploughed ground and bitumen surfaces, such as sealed runways, absorb and radiate a large amount of heat. If there are neighbouring surfaces, which absorb and radiate less heat, then local updrafts and downdrafts will form, which may strengthen throughout the day.
The pilot considered that a go-around from short final, with an engine failure to be the worst-case scenario when flying the Fairchild SA226TC. The short field approach required a VREF below the published VMC and therefore, when they planned their flight to Theodore, they utilised the normal approach profile speed of VREF 1.3 Vs0 to provide a safety margin.
The pilot calculated a LDR, from the AFM, for a short field and normal approach, which were both less than the landing distance available. When the pilot applied the factor of 1.43, the normal approach LDR was greater than the landing distance available. The pilot also knew from their previous experience, that there was a downslope on runway 17 at Theodore, which increased their LDR relative to a level runway. Therefore, the pilot always applied full reverse thrust whenever they landed the aircraft on runway 17 at Theodore. Their previous experience of using full reverse thrust on landing from a normal approach, led them to expect an actual landing distance about 100 m longer than required for a short field approach and within the Theodore landing distance available.
The pilot’s knowledge of the landing distance required and downslope of runway 17, led them to select the first row of runway lights as their aim point marker, while maintaining a 3° approach path profile. The use of this aim point resulted in the aircraft descending below 50 ft prior to reaching the runway threshold and therefore a low approach path on short final.
The time of the incident was near the end of a hot day with light winds. The pilot did not report that any airspeed fluctuations occurred during the approach, but they experienced sink early on the final approach and again when the incident occurred. Therefore, the runway undershoot was probably the result of a low approach path, which combined with a downdraft from local convective activity to lead to an early touchdown. The early touchdown resulted in the collision with a runway light and subsequent damage to the aircraft wing.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The pilot flew an approach path with a low runway threshold height, which combined with a downdraft from local convective activity on short final, resulting in a runway undershoot, collision with the runway light and damage to the aircraft wing.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they have taken the following safety actions:
Internal investigation
The operator conducted an investigation into the incident, where a detailed safety report was produced. The report concluded that ‘this incident was a mishandled landing, with the pilots’ aiming point and probable thermal activity as contributing factors.’
Training
Prior to further operations in this aircraft type, the incident pilot was retrained on the aircraft type, which involved the following:
The pilot received a detailed briefing covering aircraft type performance.
The pilot flew with the type specialist for re-training. These flights involved operations into different airports and runway environments.
The pilot was returned to duty on charter operations under supervision, and then re-assessed prior to further line flying operations.
Operations manual
The company operations manual for the Fairchild SA226TC shall be amended to reference the factoring of landing distances as a company procedure.
Safety message
This incident highlights the risk of unintended consequences associated with variations from standards. Each change on its own may not lead to an incident or accident, but may increase the likelihood of an incident or accident if combined with an unexpected event(s).
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 17 March 2017, an Agusta AB206A helicopter, registered VH-DPU, departed Caboolture Airfield, for Curtis Island, Queensland, on a private flight. On board the helicopter were the pilot and one passenger.
Prior to departure, the helicopter had been refuelled to full at Caboolture Airfield. The helicopter was flown for about 2.5 hours north, initially inland, then coastal to the north of Curtis Island where the pilot planned to land for a fishing trip (Figure 1). At 1142 Eastern Standard Time (EST), the pilot sent a text message from their[1] mobile phone to a friend monitoring their search and rescue time, which indicated they had arrived at their planned fishing spot.[2] At 1144, the helicopter was recorded on an OzRunways application, running on a mobile device, at the north-east coast of Curtis Island heading 209°.
Figure 1: VH-DPU track and accident site (drop pin)
Source: OzRunways track on Google earth, annotated by ATSB
The pilot reported that they tracked along the coast at about 500 ft and then turned the helicopter to the left from the coast to identify their planned landing site. The pilot was uncertain of the number of turns conducted near the landing site, but believed that it was during the second turn at about 50 ft and 40–60 kt that they suddenly felt there was ‘no power’. The pilot reported that the helicopter made one uncontrolled turn through about 360° during the descent, and at some stage they lowered the collective with the assumption the engine had failed.[3] The main rotor blades appeared to be flapping[4] violently to the point the pilot thought the blades were going to separate from the helicopter before impact with the water. The pilot and passenger reported that they did not see any caution lights or hear any audio alarms before or during the accident sequence.
The helicopter initially impacted upright in the water before the airframe separated from the helicopter skids, turned through 180° and rolled onto its left side (Figure 2). This placed the passenger, in the left seat, under water. As soon as movement ceased, the pilot tried to pull the passenger’s head above the water, but the passenger was initially trapped in their harness. The passenger subsequently struggled free from their harness without unfastening it. The pilot and passenger exited the helicopter, at which stage the pilot reported to the passenger that they felt paralysed below the waist.
Figure 2: VH-DPU accident site at low tide
Source: Queensland Police Service
The pilot and passenger decided to attempt to retrieve the emergency position indicating radio beacon (EPIRB),[5] which was located in a bracket mount on the passenger side of the helicopter, which was under water. On their third unsuccessful attempt to retrieve the EPIRB, the pilot became temporarily entangled with the helicopter controls and headset under water and no further attempts were made. The passenger then assisted the pilot, who was unable to move their legs, to above the high tide mark along with the provisions they could retrieve from the helicopter, which included a first aid kit.
On 18 March 2017 (the next day), a member of the public sighted debris north of Curtis Island, which they reported to the police. The recovery of the debris revealed the name of the accident passenger’s daughter. When the police contacted the passenger’s family, the family told the police the helicopter was overdue. The Australian Maritime Safety Authority then coordinated the search, which included use of OzRunways data. Although the pilot could see the search and rescue services within their vicinity at times during the search period, they could not signal them. At about 0300 on 19 March 2017, the rescue helicopter located the wreckage and survivors, who were transferred to Rockhampton Hospital. The pilot and passenger were seriously injured, and the helicopter was substantially damaged.
Fuel on board
The helicopter was originally manufactured with a standard 288 L fuel tank and was subsequently modified with a fuel range extender device, which increased the fuel tank capacity to 344 L. The standard fuel refill port is not located at the top of the fuel tank. The range extender is an L-joint device fitted to the refill port, which raises the height of the refill port to increase the capacity of the fuel tank. It was reported that the helicopter was refuelled to full fuel (344 L) with the addition of 212 L on the morning of the accident by the pilot’s maintenance provider. The pilot did not visually inspect the fuel quantity, but noted the fuel gauge indicated full when power was applied to the helicopter.
The manufacturer calculated the helicopter would consume about 100 L per hour of fuel. If the helicopter had full fuel at departure, the manufacturer estimated that after 2.5 hours of flight there should have been about 94 L of fuel on board. This is greater than the quantity of fuel which would activate the low fuel level caution light, which is about 76 L. The pilot reported that the fuel gauge indicated about 25 gallons (95 L) when they conducted their pre-landing checks, and the low fuel caution light did not illuminate during the flight. The passenger reported a strong smell of aviation fuel in the water immediately following the accident.
Examination of the wreckage
The aviation loss surveyor appointed by the insurer recovered the helicopter wreckage from Curtis Island to Rockhampton for an initial examination. They found the fuel tank ruptured and fuel present in the fuel filter, which is located in the fuel line between the fuel tank and the engine. They followed the fuel line to the engine fuel control unit and found fuel present on both the inlet and outlet side of the unit. They inspected the engine inlet and outlet and did not find any obvious damage. They noted one of the rotor blades had very little damage, which indicated to them that there was little rotational energy in the rotor blades at the time of impact.
The surveyor subsequently conducted further detailed inspections of components and parts. They found the drives for the fuel pump, fuel control unit and governor were intact. The engine and transmission chip detectors and filters for the fluid systems (fuel, oil and hydraulic) revealed no evidence of a mechanical failure.
ATSB review of photographic evidence
The Queensland Police Service provided a considerable number of photographs of the wreckage to the ATSB. On review of the photographs, the ATSB could not identify any obvious mechanical fault with the helicopter that was not attributable to accident impact damage. The overhead circuit breaker panel had several tripped circuit breakers, including the warning lights, audio panel and instrument lights circuit breakers. However, it is possible for circuit breakers to trip as a result of impact forces.
Testing the warning and caution lights, and checking the overhead circuit breakers, are items in the flight manual checklists for before and after engine start. The pilot reported that these checks were performed before departure from Caboolture. They made radio transmissions during the flight and communicated with the passenger using headsets, which indicates that the audio circuit breaker was in prior to the accident. The ATSB noted that the condition of the main and tail rotor blades indicated there was little rotational energy in the blades at the time of impact (Figure 3).
Figure 3: VH-DPU main and tail rotor blades
Source: Queensland Police Service
Engine out warning
The helicopter was fitted with an ‘engine out’ warning light and audio alarm (horn). The warning activates at 55 (+/- 3) per cent engine gas generator speed. Activation of the warning light is checked when the battery is switched on in the engine pre-start check. The pilot reported that this was checked serviceable before the accident flight in accordance with the checklist. The pilot and passenger reported that they did not observe any warning lights or hear any alarms during the accident sequence. The ATSB inspected the ‘engine out’ light bulb and found no evidence of stretching or ductile failure. Substantial impact force is required to damage a light bulb filament and a hot filament will sustain damage at a lower force than a cold filament. The absence of damage to the filament, by itself, is inconclusive.
Torque effect
The AB206A helicopter engine drives the main rotors to the left, when viewed from the pilot’s seat. This subjects the airframe to a turning moment to the right (Figure 4). The tail rotor provides the anti-torque force to prevent the engine power from turning the airframe to the right. It is mechanically connected to the main rotor system through the main rotor gearbox and operates at a speed, which is much higher, but proportional to the main rotors. A reduction in rotor speed will reduce the anti-torque force provided by the tail rotor and can lead to loss of tail rotor effectiveness and consequently loss of directional control.
Figure 4: General effect of engine torque
Source: Bell Helicopter, annotated by ATSB (Agusta AB206A rotors turn in the same direction)
Rotor stalls
During a powered descent, or a descent following an engine failure, the helicopter experiences a rate of descent airflow in opposition to the rotor induced airflow.[6] This can increase the rotor blade’s angle of attack[7] to the point that the root of the blades may stall.[8] Decaying rotor speed is the initial indication. If the pilot does not respond to the early symptoms by lowering the collective, then the stalled region spreads outward towards the rotor tips. A complete rotor stall will lead to a loss of directional control, severe blade flapping and possible blade failure from high blade coning angles.[9]
Further information on rotor stall and how to recover from low rotor speed is available from the United States Federal Aviation Administration Helicopter flying handbook, chapter 11: Helicopter emergencies and hazards.
Pilot reaction to low rotor speed
If a high collective setting is in use, then the rotor blades will have a high pitch setting with associated high rotor drag. In the absence of power, or with insufficient power, the high drag will reduce the speed of the rotors.
The research was conducted in response to three recommendations from fatal helicopter accidents in the UK in 1981, 1986 and 1992. The accidents were associated with low rotor speed at impact.
The UK CAA found that ‘pilots immediately detected failures involving variables within their focus of attention, but required more time to detect alerting cues outside their focus of attention.’ It also found that ‘auditory cues were probably the most significant alerting stimuli in each type of helicopter, and some differences in detection times correlated with the degree to which auditory cues were ‘attention getting’.’
Low rotor speed warning
The AB206A helicopter flight manual emergency procedures section included the following details within the caution system:
Fault and remedy: Rotor RPM is below normal. Reduce collective pitch and check that throttle is full open.
The 206A was manufactured by Agusta,[11] in Europe, and by Bell Helicopter in North America and Canada. The accident helicopter was an Agusta AB206A, manufactured for the Austrian Army in 1969 and registered in Australia on 7 April 2011. The pilot was unsure if the helicopter was fitted with a low rotor speed warning system, but the former owner reported that it was not fitted. The manufacturer reported that at the time of the delivery of the helicopter from production, the low rotor speed warning system was not fitted to the AB206A helicopters. Bell Helicopter have published approved data to retrofit a low rotor speed warning system to some serial numbers of their 206A helicopters (service instruction 206‑74), but there is currently no approved data to retrofit a low rotor speed warning system to the Agusta AB206A.
Certification specifications
The accident helicopter was operating under the Civil Aviation Safety Authority type acceptance certificate for the AB206A, which referenced the European Aviation Safety Agency (EASA) issued type certificate data sheet for the certification specifications (CS). VH-DPU was manufactured in 1969 in Italy to the United States (US) Civil Aeronautics Board[12] standard Civil Air Regulations Part 6 (CAR 6) Rotorcraft airworthiness: normal category, dated 20 December 1956.
Current EASA (CS-27) and US Federal Aviation Administration (27.33) certification specifications for ‘Main rotor speed and pitch limits’ include the following:
For each single engine helicopter…there must be a main rotor low speed warning.
In accordance with CS 27.33 (e) (1) and (3):
The warning must be furnished to the pilot in all flight conditions…when the speed of a main rotor approaches a value that can jeopardise safe flight, and, a visual device that requires the attention of the crew within the cockpit is not acceptable by itself.
The CAR 6 standard did not require the installation of a low rotor speed warning system, only instrument markings to indicate the limits beyond which operation is dangerous. Nevertheless, from the AB206B model, the low rotor speed warning system was factory installed as standard.
Previous accidents
Low rotor speed
The ATSB investigation of a forced landing involving a Robinson R44 helicopter (AO-2016-172) on 17 December 2016 indicated that the pilot was alerted to a low rotor speed condition by the associated warning horn. The pilot noted the rotor speed had reduced to 85 per cent at the time the warning directed their attention to the rotor speed. They were conscious of a potential rotor stall condition if they allowed the rotor speed to reduce below 80 per cent while they positioned the helicopter for an autorotation to a safe landing site.
Active noise reduction headsets
The pilot of VH-DPU was wearing an active noise reduction (also known as noise cancelling) headset and was not alerted to any unusual noises before they experienced what they described as ‘no power.’ Several pilots involved in previous accidents have commented that the use of these headsets may have impeded their ability to hear aircraft warning devices or the early signs of an impending mechanical failure.
For further information see the following ATSB reports:
In 2013, the ATSB published a report on the effectiveness of emergency locator transmitters (ELTs) in aviation accidents (AR-2012-128). ELTs are radio beacons carried on aircraft so that in the event of an accident in a remote location the wreckage and survivors can be located quickly by search and rescue services. This increases the chances of survival for the occupants. The report included personal locator beacons (PLBs) and EPIRBs.
Airframe mounted ELTs are designed to automatically activate during a crash, by a g-force activated switch or, less commonly, by a water-activated switch. The report identified safety concerns regarding the operation of ELTs and found that they functioned as intended in about 40–60 per cent of accidents in which their activation was expected. The report indicated that carrying a PLB (or EPIRB) in place of, or as well as, an airframe mounted ELT will most likely only be beneficial to safety if it is carried on the person, rather than being fitted or stowed elsewhere in the aircraft.
Safety analysis
Accident sequence
The potential wind effect on the helicopter just prior to the accident sequence was not analysed due to the pilot’s uncertainty[13] in the number of turns prior to and during the accident sequence and their report of light wind conditions leading up to the accident. The pilot reported that during the approach to land, there was suddenly ‘no power’ and that they experienced a sudden engine failure. However, the ATSB notes that the symptoms reported by the pilot were similar to the symptoms of a rotor stall.
If a helicopter is in an incipient rotor stall and the pilot either maintains or increases collective, the rotor stall will deepen. In this situation, the helicopter will not respond in the normal and expected manner, instead, rotor speed will decay and the rate of descent will increase. This response by the helicopter could be perceived by the pilot as a loss of power.
During the accident sequence, the airframe separated from the helicopter skids and turned 180°, which indicates that there was a turning moment (torque) on the airframe at touchdown. This is consistent with the pilot’s report that the helicopter rotated during the accident sequence. In the event of an engine failure, there will be no turning moment from the engine applied to the airframe. Any turning moment from the tail rotor is easily corrected and becomes negligible at low rotor speed. However, in a rotor stall the engine continues to apply torque to the airframe, which results in an uncommanded turn at low rotor speed.
The separation of the airframe from the landing skids, and final relative position of the airframe and landing skids, was consistent with low forward speed and engine torque combined with low rotor speed at impact. Therefore, the accident was probably the result of a rotor stall, but it was not determined how the helicopter entered the rotor stall. From the evidence available, fuel starvation or fuel exhaustion were considered unlikely.
Caution system
The pilot checked the circuit breakers and tested the caution and warning lights before take-off. Therefore, the circuit breakers, which were found out post-accident, probably tripped as a result of the impact forces. The results of the analysis of the ‘engine out’ light bulb were inconclusive but did not contradict the findings of the aviation loss surveyor, who found no evidence of pre-impact mechanical fault. Of note, the pilot was using an active noise reduction headset. Active noise reduction headsets could impair a pilot’s ability to hear a warning horn, such as the ‘engine out’ warning,[14] which is not transmitted through the intercom system, or any subtle pitch changes in rotor speed or engine speed. However, the ATSB did not perform any tests to evaluate this effect.
Low rotor speed warning
Previous research has found that auditory cues can reduce pilot detection time of a problem in an emergency. The current European and United States airworthiness standards for this category of helicopter require a main rotor low speed warning system, but this was not required for the accident helicopter, which was manufactured to 1956 standards. The pilot did not identify a low rotor speed condition before they experienced ‘no power’ and the helicopter was not fitted with a low rotor speed warning system.
The condition of the rotor blades post-impact indicated there was little rotational energy in the blades at the time of impact. The helicopter could lose rotor speed due to either an engine failure or rotor stall condition. In each case, other than an engine failure close to the ground,[15] the pilot should lower the collective to maintain or recover rotor speed.
It is probable that the helicopter had entered an incipient rotor stall while the pilot’s attention was focused on positioning the helicopter for their intended landing site. In the absence of a low rotor speed warning this was initially undetected until the pilot suddenly experienced ‘no power’, at which stage there was insufficient height to recover. Therefore, the absence of a low rotor speed warning system increased the risk of a loss of control.
Emergency position indicating radio beacon
The helicopter was carrying an emergency position indicating radio beacon (EPIRB), which must be manually activated. However, the pilot was unable to locate and retrieve the beacon from the wreckage in order to activate it after the accident. The pilot reported their arrival at their intended landing spot before the accident occurred, which, in combination with their inability to retrieve and activate the beacon, resulted in a considerable delay after the accident before search and rescue was activated.
The pilot and passenger were found by search and rescue services about 39 hours after the accident. Therefore, the absence of an automatically activated emergency locator transmitter (ELT) and the inability of the occupants to retrieve their EPIRB increased the risks associated with their post-accident survival.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
It is probable the helicopter experienced a main rotor stall from a low height and low forward speed.
The helicopter was not fitted with a low rotor speed warning system. A low rotor speed warning system was not a certification requirement for the helicopter at the time of manufacture and there is currently no approved data for the modification. The absence of a low rotor speed warning system increased the risk of the pilot losing control of the helicopter.
The helicopter was carrying an emergency position indicating radio beacon which was inaccessible after the accident. This resulted in a considerable delay to the search and rescue.
The pilot reported a sudden loss of power. However, examination of the wreckage by the aviation loss surveyor found no evidence of pre-impact mechanical fault. Fuel starvation or fuel exhaustion were considered unlikely.
Safety message
The pilot reported that it was beneficial to have a first aid kit on board the helicopter, which they retrieved and used following the accident. However, they considered it necessary to carry the emergency position indicating radio beacon on the person, rather than fitted to the helicopter. They further noted that a high quality strobe light would have assisted them to signal their location once search and rescue services were in the vicinity.
The use of active noise reduction (noise cancelling) headsets has become prevalent in aviation. It is, however, important to always consider their compatibility with the aircraft warning systems. The Civil Aviation Safety Authority have published an airworthiness article (previously an airworthiness advisory circular) AAC 1-43 Noise isolating headsets, which highlights the potential benefits and risks associated with the use of these headsets.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 17 March 2017, a Saab 340B aircraft, registered VH-NRX, was operated by Regional Express (Rex) as flight RXA768 on a routine passenger flight from Albury, New South Wales (NSW) to Sydney, NSW. On board the aircraft were 16 passengers and three crew.
About 102 km (55 NM) south-west of Sydney Airport, the crew noticed uncommanded engine indications and began the necessary checklists. While undertaking the checklist items, the crew experienced minor vibrations from the right engine. These vibrations worsened as the checklist progressed and became visually evident to the first officer. As a result, the crew commenced the engine shutdown procedure. During the procedure, the propeller separated from the aircraft. The crew made a PAN PAN[1] call to air traffic control, and completed the engine shutdown procedure. The aircraft landed without incident at Sydney Airport.
On 21 March 2017, the NSW Police Aviation Support Branch located the propeller in an area under dense forest about 19 km (10 NM) south-west of Sydney Airport.
What the ATSB found
An inspection of the aircraft by the ATSB at Sydney Airport identified that the propeller gearbox (PGB) propeller shaft had fractured, leading to the separation of the propeller. Subsequent laboratory analysis of the propeller shaft revealed that the failure occurred as a result of a fatigue crack that had initiated from the PGB propeller shaft flange dowel pin hole.
The ATSB found that the manufacturer’s maintenance documentation did not include specific inspection procedures to detect fatigue cracking of the propeller shaft. In addition, the operator’s inspection worksheets did not provide for the recording of inspection findings as defined within documented procedures. Consequently, this may not have provided for the best opportunity to ensure potential defects were identified, recorded and monitored.
What's been done as a result
Following the occurrence, the engine manufacturer (General Electric) released a number of service bulletins (SB 72-0530 and SB 72-0531) requiring immediate inspection of the PGB propeller shaft. Changes were also made to the engine maintenance manuals to include more ongoing detailed inspections of this area. Additionally, the United States Federal Aviation Administration, issued airworthiness directive AD 2018-03-13, on 14 February 2018, which required initial and repetitive visual inspection and fluorescent-penetrant inspection (FPI) of the main propeller shaft for affected engines.
Safety message
This occurrence highlighted how non-life-limited components such as a propeller shaft may still develop defects and fail in-flight. Appropriate training, the use of checklists and effective crew interaction, provide the best opportunity for a positive outcome in the event of such a failure affecting flight safety. Additionally, operators are reminded of the importance of having worksheets that accurately reflect the requirements and intentions of associated maintenance documentation.
On 17 March 2017, a Saab 340B aircraft, registered VH-NRX was operated by Regional Express (Rex) as flight RXA768 on a routine passenger flight from Albury, New South Wales (NSW) to Sydney, NSW. On board the aircraft were 16 passengers and three crew.
About 109 km (55 NM) south-west of Sydney Airport, the crew noticed a slight fluctuation on the right engine torque gauge. The captain manipulated the power levers and condition lever to see if that could rectify the condition. When those actions were unable to stop the fluctuations, the crew proceeded to action the uncommanded engine operation procedures. While undertaking the checklist items, the crew experienced minor vibrations from the right engine. These vibrations worsened as the checklist progressed and became visually evident to the first officer. As a result, the crew commenced the engine shutdown procedure. During the engine shutdown procedure, at 1149 AEDT[2], the propeller separated from the aircraft. The crew made a PAN PAN[3] call to air traffic control, and completed the engine shutdown procedure. The aircraft landed without further incident at Sydney Airport.
Figure 1: The aircraft, VH-NRX, at Sydney Airport after the incident showing the point of separation of the propeller in close-up
Source: Grahame Hutchison and ATSB (modified)
An inspection of the aircraft by the ATSB at Sydney Airport identified that the propeller shaft had fractured, leading to the separation of the propeller.
On 21 March 2017, the NSW Police Aviation Support Branch (PolAir) located the propeller in an area under dense forest about 19 km (10 NM) south-west of Sydney Airport. The propeller was found with the flange section of propeller shaft secured to the propeller assembly and a fracture through the propeller shaft (Figure 2).
Figure 2: The separated propeller from VH-NRX
This image shows the propeller as found in bushland by PolAir about 19 km (10 NM) south-west of Sydney Airport.
This shows the propeller flange still attached to the rear of the propeller. Note that the attachment nuts were in the process of being removed by ATSB investigators onsite, in order to release the flange.
The ATSB downloaded and analysed data from the aircraft’s flight data and cockpit voice recorders (FDR and CVR, respectively). The data confirmed the crew had identified problems with the right engine torque gauge approximately 10 minutes before the failure of the propeller shaft and were in the process of actioning the relevant checklists when separation of the propeller from the aircraft occurred.
Personnel information
Both the captain and first officer held valid Class 1 medical certificates, and were appropriately qualified to conduct the flight. The captain had a total aeronautical experience of 6,631 hours, with 2,788 hours flying Saab 340 aircraft. The first officer had a total aeronautical experience of 1,683 hours with 1,410 hours flying Saab 340 aircraft.
Crew actions
Following the onset of the torque gauge fluctuations, the flight crew used the relevant the checklists, and worked together well as a crew. The crew did not divert from the checklists, and used additional services from air traffic control to manage the aircraft. The crew did not make any rapid decisions, and ensured that all options were considered before action was taken, including consideration of the go-around requirements due to weather.
Aircraft and engine information
The aircraft was a Saab 340B aircraft, serial number 340B-291, manufactured in 1991 and first registered in Australia in October 2004. At the time of the occurrence, the airframe had accumulated 39,625 hours and 43,112 flight cycles total time in service.
The aircraft was fitted with two General Electric (GE) CT7-9B turboprop engines. The CT7 engine consists of a modular power unit and a propeller gearbox (PGB). The engine can be fitted with a Dowty or Hamilton Sundstrand propeller.
The propeller separated due to cracking between the propeller main shaft and the flanged region (Figure 3) on the right side PGB.
Figure 3: Propeller gearbox schematic highlighting the recovered section of the propeller shaft
Source: GE Aviation, modified by ATSB
The operator imported the event PGB module—serial number UDAG0153—from an international operator in December 2015. It entered service in Australia in March 2016 following fitment to the event engine—serial number (ESN) 785150—on 8 March 2016 on another company aircraft. The assembly—ESN 785150 and PGB UDAG0153—with Dowty propeller SN DRG/7635/91 was fitted to the right side of VH-NRX on 16 November 2016. At the time of the occurrence, the PGB had accumulated 46,406 hours (TSN) and 42,872 flight cycles since new (CSN).
Propeller shaft examination
Failure of the propeller occurred as a result of cracking between the propeller main shaft and the flanged region.
The propeller was found attached to the forward-facing (mating) flange by 12 self-locking nuts and two dowel pins, which are a press fit into the dowel pin holes. Following removal of the bolts, the fractured section of the propeller shaft was removed. The dowel pins were still installed in their respective dowel pin holes, and the non-metallic gasket/shim located between the propeller shaft flange and the propeller hub did not exhibit any wear or damage. The flange section of the propeller shaft was sent to the ATSB’s Canberra facilities for further examination (Figure 4).
Figure 4: Separated shaft section in their as-received condition
Image shows that cracking was observed near one of the dowel pins and the fretting discolouration observed on the propeller side of the flange. Source: ATSB
Examination of the propeller flange section of the fractured shaft revealed cracking emanating from one of the dowel pin holes (Figure 4). The cracking had progressed through the flange thickness, transitioning into the shaft portion at an angle indicative of torsional loading, and ultimately resulted in shaft separation. The shaft fracture had deformed in a radial direction, which exposed some of the fracture face, and evidence of beachmarks typical of fatigue (cyclic) cracking were observed (Figure 5).
Figure 5: Section of the exposed propeller shaft showing beachmarks
Image shows the beachmarks on the fracture surface, which was indicative of a fatigue failure mechanism. Source: ATSB
Local fretting damage and corrosion was observed around the forward flange surface circumference with the more severe damage observed directly inboard of the dowel pin hole at the crack location. Remaining flange thickness in the more heavily fretted region measured 0.684 inch (17.37 mm), which was 0.03 mm below the minimum manual limit requirement of 0.685 inch (17.40 mm). An oily dark residue was present around the retention lip feature of the dowel pin hole.
Similar shaped discoloration patterns to those observed on the propeller shaft forward flange were present on the gasket/shim; however, negligible wear was measured in these regions. Gasket/shim thickness measured 0.060 inch (1.524 mm) in two areas, indicating fretting wear on the steel propeller shaft likely occurred prior to the introduction of this particular gasket/shim. The gasket/shim is retained with the propeller during the removal/installation procedure, and the maintenance manual does not contain any information on when it is required to be changed. As such, there was no record of when this gasket/shim had been installed on that propeller.
Following the initial visual examination, the sample was sectioned through the dowel pin holes in order to expose the fracture surface (Figure 6). Once opened, a discoloured initial fracture region consistent with fatigue was observed towards the forward flange face along with some discoloration of the dowel pin itself. The fatigue fracture itself had completely progressed through the flange thickness.
Figure 6: Section of the propeller shaft showing the fatigue crack progressing into the shaft
Source: ATSB
The dowel pin bore was corroded in parts (shown in Figure 7), and corrosion pitting was found near the fracture. Cadmium (Cd) plating, normally present on the forward flange face, dowel pin hole surfaces and exposed propeller shaft, was missing within the dowel pin hole, with the exception of several streaks near the aft end of the hole.
Figure 7: Corrosion observed within the bore of the dowel pin hole
Image show corrosion in bore, along with crack originating at the forward corner of the dowel pin hole (arrowed) Source: ATSB
Manufacturer’s materials failure analysis
Following the visual examinations and preliminary sectioning at the ATSB facilities, the fractured components were returned to the engine manufacturer for additional analysis and testing. Examination in a scanning electron microscope confirmed the presence of corrosion product immediately below the initial fracture region along with shallow, trough-shaped features (Figure 8). Corrosion pitting was observed along the edge of the initial fracture leading to a rounded appearance. Spectral imaging (energy dispersive x-ray analysis) of the dowel pin hole and fretted region on the propeller shaft flange forward face also confirmed the absence of original cadmium (Cd) plating. The corrosion product consisted of iron (Fe), oxygen (O) (consistent with a steel corrosion product) sulphur (S) and residual cadmium (Cd).
Figure 8: Scanning electron microscope image of the internal surface of the dowel pin hole and initial fracture surface
Source: GE
The propeller shaft flange was then sectioned to perform a microstructural examination of the fracture surface and the adjacent area. No microstructural anomalies were observed, and the microstructure was tempered martensite, consistent with the material type in the correctly processed condition. However, the metallographic sections showed significant general surface corrosion, pitting corrosion and secondary cracking in the area adjacent to the primary fracture surface. Many of the shallow secondary cracks identified during a step polishing examination were filled with corrosion product (Figure 9). The presence of multiple shallow crack features supported crack initiation towards the forward dowel pin hole area.
Figure 9: Metallographic cross section adjacent to the fracture surface showing secondary cracking
The micrograph shows the secondary cracking extending from the dowel pin hole in the region adjacent to the primary fracture surface. Also, note the corroded initial fracture surface at the top of the image, and the rounded fracture edge. Note that 2 mil is approximately equal to 50 µm. The crack length in the image is approximately 84 µm in length. Source: GE
Due to the badly corroded condition of the initial fracture surface, the engine manufacturer was unable to establish a definitive contributing factor for crack initiation. It was considered that corrosion within the dowel pin hole was a strong contributor. However, stress analysis performed by the manufacturer confirmed low alternating stresses in dowel pin hole area. For a flaw of 3.8mm x 3.8mm, with nominal assumptions, it was predicted that there would be no crack propagation. That is, corrosion pitting down to depth observed in the dowel pin hole on its own, would not cause crack propagation.
Mechanisms that would increase the dowel pin load such as loss of clamp between the flange faces could assist in crack initiation. While the torque values were not recorded during flange removal from the recovered propeller, bolt tensions were observed to be similar for all bolts and were consistent with expectations. Additionally, while the operator did not record torque values as part of their propeller removal process (nor were they required to per the propeller maintenance manual), they did not report experiencing any instances of low bolt tension during the propeller removal process.
The presence of that significant secondary corrosion did, however, support either an initially slower moving crack or a crack that had arrested for some unquantifiable period allowing the corrosion to occur. The remaining, less damaged portion of the fracture surface was consistent with lower alternating stress, high cycle fatigue (HCF) mechanisms, ultimately leading to shaft separation.
Propeller gearbox maintenance
Maintenance of the PGB propeller shaft was on-condition, meaning no mandated maintenance activities were specified, as it was a non-life-limited component. There were no records of shop visits for repair of PGB UDAG0153. There were also no records of animal strikes or propeller events.
The maintenance documentation did require ongoing inspection of the main propeller shaft whenever the gearbox was returned for maintenance. The GE maintenance manual SEI-576 72-10-00 also stated that whenever the propeller flange was exposed, for example, a propeller change, it was to be inspected for the following:
nicks, burrs and scratches
usable limits: any number, 0.15 inch (0.38 mm) deep maximum
corrective action: remove high metal
elongated holes
usable limits: none allowed
corrective action: replace gearbox
dowel deformation
usable limit: not permitted
corrective action: replace gearbox
missing cadmium plating on:
forward face of the flange
usable limit: any amount with no corrosion
corrective action: replace gearbox
other locations
not permitted, if base metal visible
corrective action: repairable, brush with cadmium
wear on the face of the flange
usable limit: flange thickness at worn area must be 0.685 inch (17.40 mm) minimum
corrective action: replace gearbox.
The most recent opportunity for the flange to be inspected was at a propeller change on 20 October 2016, approximately 5 months and 437 hours / 516 flight cycles prior to the occurrence. No rejectable issues were reported. The inspection was included in the operator’s propeller removal/installation worksheet, HM-26 Revision 5. One entry related to inspection of the flange, stated:
Carry out visual inspection of PGB propeller drive shaft flange (MRB 721003)
The worksheet contained a single box to be signed and dated at the completion of the task.
MRB 721003 was a task in the aircraft Maintenance Review Board report, which specified a ‘Visual inspection of the PGB propeller drive shaft flange during exposure at propeller maintenance’ and referred to GE MM SEI 576 72-10-00.
This particular PGB was subject to Airworthiness Directive AD 94-17-16 and Service Bulletin SB 72-A0350, Engine – General – Recommended Inspection of Propeller Shafts for Possible Inclusions. The service bulletin and supporting airworthiness directive required a one-time ultrasonic inspection of the propeller shaft flange outer diameter (OD) fillet radius and inner diameter (ID) bore to look for subsurface metallurgical defects on a suspect population of propeller shafts. The inspection was carried out on UDAG0153 on 8 February 1994 with no findings reported.
Propeller balancing
The manufacturer’s maintenance documents required a static balance of the propeller following overhaul (7,500 hours or 5 years) or major repair. The operator’s system of maintenance also required periodic dynamic balancing of propellers every 2,000-flight hours of operation. There was no requirement from the manufacturer to perform a dynamic balance upon installation of the propeller following an overhaul.
The occurrence propeller was statically balanced on 19 October 2016, at 1,361.8 hours since overhaul (TSO), as a result of fitment of a new de-ice boot. Following this maintenance activity, the propeller was fitted to PGB UDAG0153, which was installed on another company aircraft, VH-ZLX. The entire assembly (engine, PGB and propeller) was then moved to VH-NRX on 16 November 2016.
Other occurrences
The same propeller gearbox design was fitted to multiple variants of the CT7 engine (5A2, 7A1, 9B, 9C, and 9C3) on Saab 340 and EADS CASA[4] CN-235 aircraft. On 21 November 1991, a Comair Saab 340A aircraft experienced an in-flight propeller separation event near Buffalo, New York, United States. The National Transportation Safety Board (NTSB) examined that occurrence (NTSB No. NYC 92-I-A035) and concluded that the propeller shaft fractured as result of a fatigue crack that had initiated at an inclusion near the flange radius. Following the occurrence, GE mandated a fleet wide ultrasonic inspection to look for metallurgical inclusions at that location. They also changed the design of the shaft to include a larger radius at the fillet, which led to a reduction in stresses at that location.
The in-flight loss of propeller involving Saab 340B VH-NRX at 19 km (10 NM) south-west of Sydney, New South Wales (NSW), on 17 March 2017, was the result of the fracture of the propeller shaft on the right engine propeller reduction gearbox (PGB). The shaft fracture led to the separation of the propeller from the aircraft. The flight crew performed an uneventful single-engine landing at Sydney Airport. The crew showed a high level of professionalism in their response to the engine failure and loss of a propeller. The crew demonstrated high levels of communication and coordination, and promptly applied checklists and procedures. As such, this analysis will focus on the failure of the propeller shaft.
Propeller shaft separation
The shaft failed as a result of a fatigue crack propagation that initiated at a dowel pin hole. The crack then propagated into the shaft in a torsional manner, before failing in overstress.
Extensive corrosion and fretting was observed on the PGB propeller shaft forward flange surface. The initial fracture surface adjacent to the dowel pin hole corner exhibited a darker surface from corrosion and debris product compared to the remaining fracture. The corroded condition of the initial fracture surface suggested the fatigue crack had been present for a significant period. However, the time from when it initiated could not be quantified. The portion of the fracture slightly beyond the heavily corroded region was smeared, but also exhibited significant pitting corrosion. Higher magnification examination in these areas revealed general fracture morphology consistent with lower alternating stress, high cycle fatigue (HCF) crack propagation mechanisms.
Due to the corroded condition of the initial fracture surface, a definitive root cause for crack initiation could not be established, although corrosion within the dowel pin hole was believed to be a strong contributor to crack initiation. Analysis by General Electric indicated that the initiation of fatigue cracking of the flange may be associated with a combination of factors that include:
the accumulation of significant operational hours for the PGB
the development of pitting corrosion damage within the dowel pin bore and at the front face of the propeller flange
progressive wear and subsequent surface damage of the hub flange at stress-critical regions surrounding the dowel pin
possible dowel pin load increase due to reduced clamping force.
Propeller gearbox maintenance requirements
At the time of the occurrence, there were no specific requirements in the manufacturer’s maintenance documentation for routine inspection within the dowel pin bores and cracking in that location. A failure in a similar location in 1991 prompted a one-off ultrasonic inspection for inclusions in the area, however, there were no ongoing inspections required.
While the maintenance manual did specify some general inspection and measurement of the propeller flange, there was no specific task to look for cracks, such as a magnetic particle or dye penetrant inspection. These techniques were only utilised when the PGB was disassembled for maintenance at a workshop specifically approved by the engine manufacturer. As such, any cracking or corrosion within the dowel pin hole may go undetected during routine maintenance.
Operator maintenance procedures
The operator was following the directions set out in the manufacturer’s maintenance documents. The operator demonstrated that they had previously rejected two PGB’s in 2007 and 2011 due to corrosion and missing cadmium plating on the propeller shaft and/or flange.
A single direction to inspect the PGB propeller drive shaft flange was included in the propeller removal/installation worksheet, HM-26 Revision 5, in accordance with the manufacturer's maintenance procedures. However, a number of deficiencies were identified in the worksheet, which meant the aircraft maintenance engineers may not have been given the best opportunity to detect a growing crack in the PGB shaft flange area. This is because:
The worksheet referred to a visual inspection; however, the task in the maintenance manual was not solely a visual inspection. If wear was observed on the face of the flange, the flange thickness required measurement and it could be no less than 0.685 inch (17.40mm).
The brief nature of the task description meant that there were no specific instructions on how the task should be carried out. For example, the method of flange thickness measurement was not specified on the form.
There was no space on the worksheet to record any findings, such as recording the flange thickness measurements or if the cadmium (Cd) plating was worn and a repair required.
Findings
From the evidence available, the following findings are made with respect to the propeller separation event involving a 340B aircraft, registered VH-NRX (NRX), which occurred about 10 NM south-west of Sydney, New South Wales (NSW) on 17 March 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
The propeller shaft failed as a result of a fatigue crack that had initiated at the dowel pin hole and propagated through the shaft until it could no longer transmit the required loads.
The engine manufacturer did not have specific inspection procedures in the maintenance documents of the propeller shaft to detect a fatigue crack originating from the dowel pin hole. [Safety Issue]
Other safety factors
The form used by Regional Express during a propeller removal and installation, HM-26 Revision 5, included the task to inspect the propeller gearbox, but did not provide for recording of inspection findings as defined within documented procedures. Consequently, this did not provide for the best opportunity to ensure potential defects were identified, recorded and monitored.
Other findings
The flight crew used checklist management and crew resource management effectively. These factors combined to contribute to a positive outcome for the aircraft.
The ATSB and the engine manufacturer, General Electric, were unable to determine conclusively the reason for the fatigue crack initiation and propagation.
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the [aviation, marine, rail - as applicable] industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.
The engine manufacturer did not have specific inspection procedures in the maintenance documents of the propeller shaft to detect a fatigue crack originating from the dowel pin hole.
Additional safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Regional Express
Following the occurrence, Regional Express (Rex) undertook a large number of actions, both in the immediate aftermath and as more information became available on the nature of the failure.
Five aircraft with the same series PGB and shafts were immediately removed from service for further examination.
The fleet-leader inspections of 12 nominated PGB’s were completed as per service bulletin SB 72-0530, by 16 June 2017.
Inspections in accordance with service bulletin SB 72-0531 were completed on 14 February 2018 (71 inspections).
The Rex Safety Management Group also approved completing the service bulletin inspection for all Rex fleet PGB’s that were outside of SB 72-0530 and SB 72-0531. As of 4 July 2018, Rex has completed a further 23 PGB inspections. On 28 February 2018, the FAA issued AD 2018-03-13, which was effective to the CT7 PGB and required the GE SB to be carried out on all PGB’s regardless of the TSN. Due to the existing propeller maintenance practices Rex had implemented and service bulletin scheduling in place, Rex was already compliant with the requirements of AD 2018-03-13. They also adjusted the scheduling of certain PGB inspections to match the AD compliance timeframe.
The previous operator of the PGB was contacted to obtain historical details of operation and maintenance.
During inspection of the propeller shaft in accordance with SB 72-0531, onsite training, including instruction from the manufacturer’s CT7 platform lead principal engineer, was conducted with line maintenance supervisors and other licensed aircraft maintenance engineers (LAMEs). In addition, computer based training (CBT) with specific reference to inspection of the propeller shaft was set up for all B1 LAMEs. The CBT will be recurring every 2 years.
The operator performed a review of the maintenance practices for propeller removal/installation as described in their worksheets, HM-26, HM-27 and HM-15. As a result, the operator identified areas of improvement and changes to the worksheets have been implemented. The worksheets have been amended to include additional inspection steps for the PGB propeller shaft based on the latest GE service bulletin, SB 72-0531. A Notice to Engineers (NOTEM) was issued to all Saab Engineers on 3 July 2017 to advise them of the worksheet revisions.
Established in-house capability to carry out the manufacturer's corrosion prevention process (cadmium (Cd) plating) through procurement of the necessary materials and equipment and training of engineering staff.
An assessment of propeller balance maintenance practices were carried out and some modifications implemented including;
Introduction of a periodic oil change task for the Hamilton Sundstrand[5] propeller hub.
A requirement to carry out a dynamic balance on each occasion that a Hamilton Sundstrand propeller blade or hub is installed.
Issuing instructions to engineers with a policy to achieve blade-shimming clearance at the lower end of the available range when installing Hamilton Sundstrand propeller blades.
Initiation of a review of the propeller balance policy for the Dowty propeller.
Civil Aviation Safety Authority
The Civil Aviation Safety Authority conducted two audits on the operator following the event; the first was carried out from 3-11 May 2017; the second on 10-11 July, specifically looking at the propeller maintenance practices of the organisation.
The sources of information during the investigation included the:
flight crew
aircraft operator (Regional Express)
engine manufacturer (General Electric)
aircraft manufacturer (Saab)
Federal Aviation Administration (USA)
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Regional Express, Civil Aviation Safety Authority (CASA), General Electric, National Transportation Safety Board (NTSB), Saab, and the Swedish Accident Investigation Authority.
Submissions were received from Regional Express, CASA, General Electric and NTSB. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Preliminary report
Report release date: 13/04/2017
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On 17 March 2017, a Saab 340B aircraft, registered VH-NRX (NRX) was being operated as RXA768 on a routine passenger flight from Albury, New South Wales (NSW) to Sydney, NSW. On board the aircraft were 16 passengers and 3 crew.
About 55 nautical miles south-west of Sydney airport, the crew noticed uncommanded engine indications and began the necessary checklists. While undertaking the checklist items, the crew experienced minor vibrations from the right engine. These vibrations worsened as the checklist progressed and became visually evident to the First Officer. As a result the crew commenced the engine shutdown procedure. During the engine shutdown procedure, the propeller separated from the aircraft. The crew made a Pan-Pan[1] call to air traffic control, and completed the engine shutdown procedure. The aircraft landed without incident at Sydney airport.
Figure 1: The aircraft, VH-NRX, at Sydney airport after the incident
Source: Grahame Hutchison
An inspection of the aircraft by the ATSB at Sydney airport identified that the propeller shaft had fractured, leading to the separation of the propeller.
On 21 March 2017, the NSW Police Aviation Support Branch (PolAir) undertook a search operation for the separated propeller. The propeller was located in an area under dense forest about 8NM south-west of Sydney airport.
Figure 2: The propeller that had separated from VH-NRX as found by PolAir about 8NM south-west of Sydney airport
Source: ATSB
The propeller was found with the flange section of propeller shaft secured to the propeller assembly and a fracture through the propeller shaft. ATSB subsequently removed the remaining propeller shaft and integral flange section (Figure 4) for examination at its facilities in Canberra.
Propeller shaft examination
The recovered part of the propeller shaft is highlighted in figure 3. The propeller was found properly secured to the forward-facing flange by bolts and the dowel pins pictured. The examination was conducted with representatives present from the Civil Aviation Safety Authority (CASA), SAAB, GE Aviation (engine manufacturer) and Regional Express (REX). Initial observations revealed cracking that appeared to run between the main shaft and the flange region. The part was sectioned in order to expose the crack’s fracture surface.
Figure 3: Propeller gearbox schematic highlighting the recovered section of the propeller shaft
Source: GE Aviation, modified by ATSB
The crack was found to be a fatigue fracture that had initiated within the propeller mounting flange, and then transitioned into the shaft section (see figure 4). The crack originated at the bore of a dowel pin near the forward face of the propeller hub flange. The dowel pin bore was corroded in parts (shown in figure 5), and corrosion pitting was found near the fracture. Further work is ongoing to ascertain whether the corrosion or other factors contributed to the fracture initiation.
Figure 4: Section of the propeller shaft showing the fatigue crack originating at the dowel hole and progressing into the shaft itself
Source: ATSB
This is the first known critical failure of this type initiating within the propeller hub flange of a GE Aviation CT7-9B engine. The same propeller gearbox (PGB) is fitted to multiple variants of the CT7 engine (5A2, 7A1, 9B, 9C, and 9C3) on SAAB 340 and EADS CASA[2] CN-235 aircraft. There is currently no maintenance requirements specified in existing maintenance manuals for routine inspection within the dowel pin bores. Any corrosion or cracking within the bore may go undetected until it progresses to the surface of the flange. Other than a visual inspection of the flange during propeller removal, inspection for surface defects (via magnetic particle inspection or dye penetrant inspection) only occurs when the PGB is disassembled for maintenance at a workshop specifically approved by the engine manufacturer.
Figure 5: Corrosion observed within the bore of the dowel pin hole
Source: ATSB
Safety advisory notice
AO-2017-032-SAN-001:
The ATSB advises that those responsible for the operation and maintenance of SAAB 340 and EADS CASA CN-235 aircraft fitted with the GE Aviation CT7 engine type variants 5A2, 7A1, 9B, 9C, and 9C3 should note the facts presented in this preliminary report with a view to addressing any risks to their own operation.
Proactive safety action taken by GE Aviation
GE Aviation is actively involved in supporting the Australian Transport Safety Bureau in this investigation. The propeller flange and all required hardware has been transported to GE Aviation laboratories in Cincinnati for further metallurgical analysis. GE Aviation is inspecting additional PGBs from the fleet and recommends that all operators follow existing maintenance and inspection procedures. As the investigation progresses GE Aviation will release additional maintenance and inspection recommendations if they become necessary.
Proactive safety action taken by Regional Express
Regional Express has quarantined all propeller gearboxes with propeller shafts of the same series as that installed in VH-NRX.
Further investigation
The investigation is continuing and the ATSB will focus on:
maintenance procedures associated with the PGB shaft
factors that may have contributed to the fatigue fracture at the propeller mounting flange, possibly including:
design and manufacturing of the dowel pins, bores, and overall assembly
corrosion protection on the surface of the part
opportunities for crack detection.
Should any critical safety issues emerge during the course of the investigation, the ATSB will immediately bring those issues to the attention of the relevant authorities or organisation. This will allow those authorities and organisations to consider safety action to address the safety issues. Details of such safety issues and any safety action in response will be published on the ATSB website at www.atsb.gov.au.
______________________
The information contained in this web update is released in accordance with section 25 of the Transport Safety Investigation Act 2003 and is derived from the initial investigation of the occurrence. Readers are cautioned that new evidence will become available as the investigation progresses that will enhance the ATSB's understanding of the accident as outlined in this web update. As such, no analysis or findings are included in this update.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.