Loss of control

Collision with terrain involving Reims Aviation F406, VH-EYQ, 3 km from Oakey Airport, Queensland, on 20 July 2025

Summary

The ATSB is investigating a collision with terrain accident involving a Reims Cessna F406 aircraft, registered VH‑EYQ, near Oakey, Queensland, on 20 July 2025.

The aircraft was being used for a pilot check flight and was conducting an instrument approach to land at Oakey Army Aviation Centre when it collided with terrain in a field approximately 2 km from the runway. The 2 occupants on board, a pilot and a flight examiner, were fatally injured.

The ATSB has commenced the examination and analysis of the initial evidence collected.

To date, the ATSB has:

  • examined the wreckage and accident site
  • examined meteorological information
  • interviewed relevant parties
  • collected radio communication, aircraft traffic surveillance data, and navigational 
    application data
  • collected aircraft, pilot, crew and operator documentation.

The investigation is continuing and will include review and examination of:

  • pilots’ recent history
  • propellers
  • maintenance records 
  • pilot and crew training and medical records
  • operational procedures and documentation
  • further interviews with relevant parties
  • flight data and air traffic surveillance data
  • the requirements of conducting simulated one engine inoperative exercises at low heights.

A preliminary report, which detailed factual information established during the evidence collection phase, was released on 10 December 2025 (see below).

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.

Last updated:

Preliminary report

Report release date: 10/12/2025

This preliminary report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

Summary video

The occurrence

On 20 July 2025, a Reims Aviation F406 Caravan II, registered VH-EYQ, was being utilised for an instrument proficiency check (IPC)[1] with a pilot and a flight examiner on board. The flight was conducted under the instrument flight rules[2] and the planned route was from Warwick Airport to Oakey Airport, Queensland, later returning to Warwick Airport. 

The IPC was the pilot’s third flight for the day. They had undertaken an aerial survey mission in VH-EYQ that morning for Aero Logistics, having departed Emerald Airport, Queensland, at 0747 and arrived at Archerfield Airport, Queensland, at 1208. The pilot refuelled the aircraft at Archerfield Airport and departed at 1308 for the flight to Warwick Airport for the purposes of undertaking the IPC. 

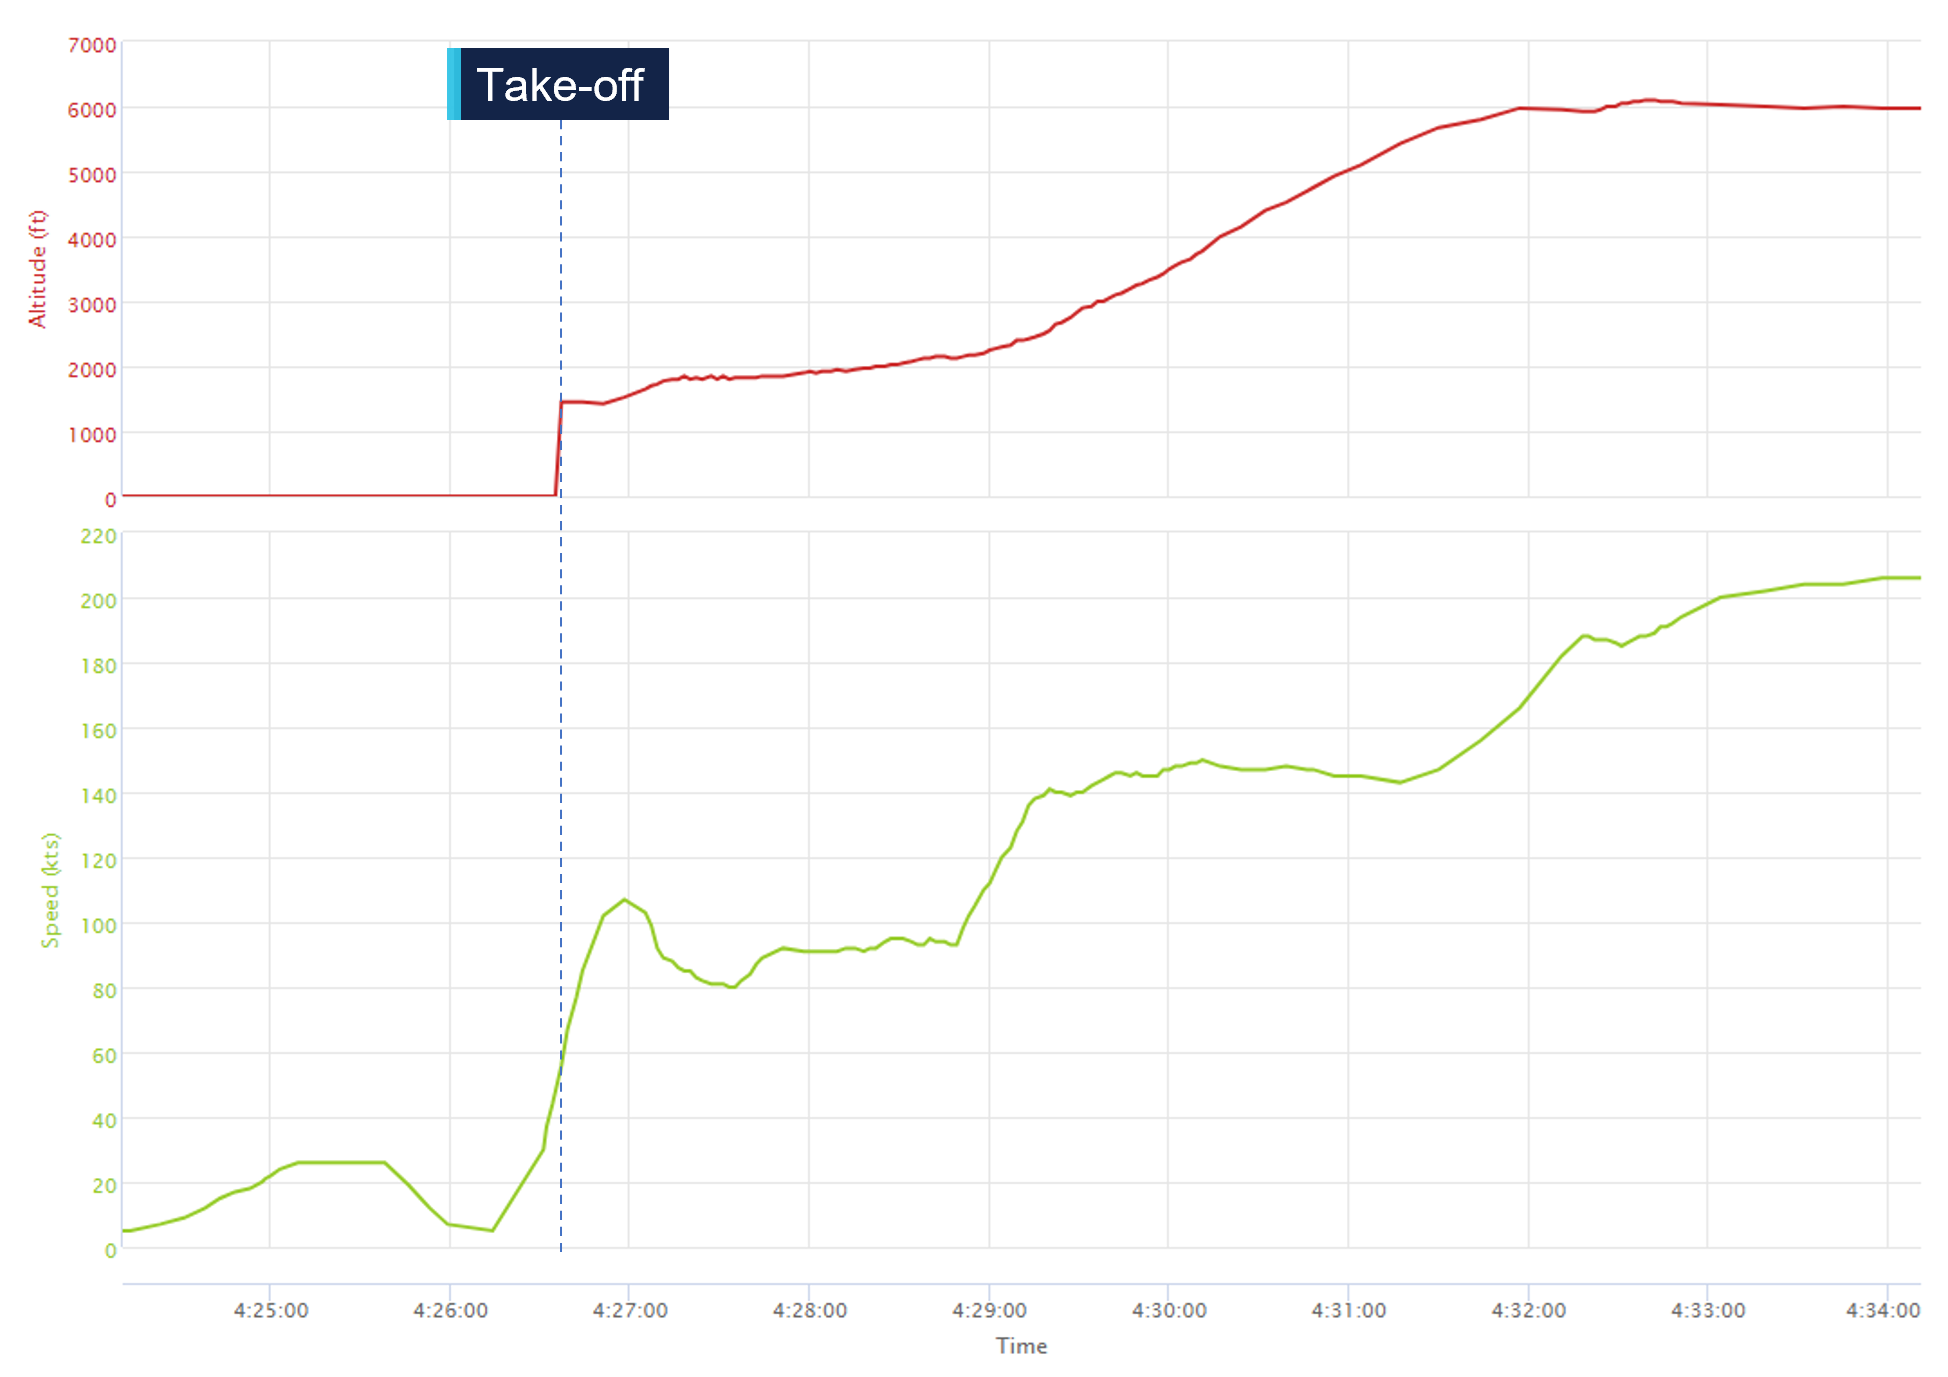
The pilot arrived at Warwick Airport at 1345 where they met the flight examiner. At 1426, the aircraft departed Warwick Airport. About 16 seconds after departure, the aircraft’s groundspeed began to decrease from 109 kt, and the aircraft stopped climbing and commenced a slow turn to the right (Figure 1). This turn was not consistent with the submitted flight plan. The aircraft’s groundspeed continued to reduce over a period of about one minute to 80 kt (see Recorded flight data). The aircraft then began to accelerate before turning left and commencing a climb to an altitude of 6,100 ft above mean sea level. 

Figure 1: VH-EYQ departure from Warwick Airport
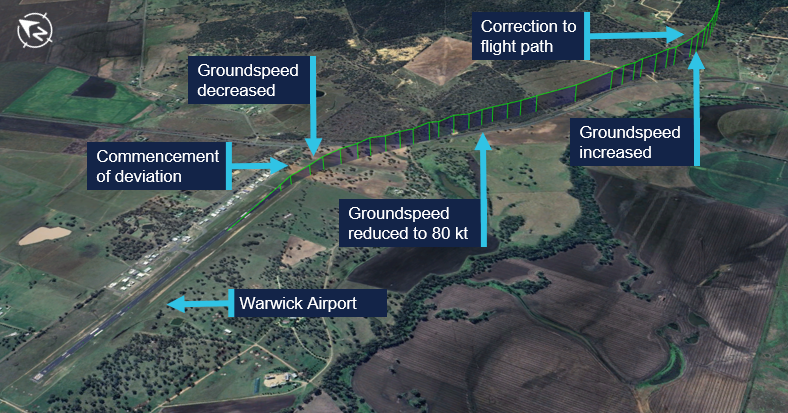
VH-EYQ departure from Warwick Airport

Source: Google Earth, annotated by the ATSB

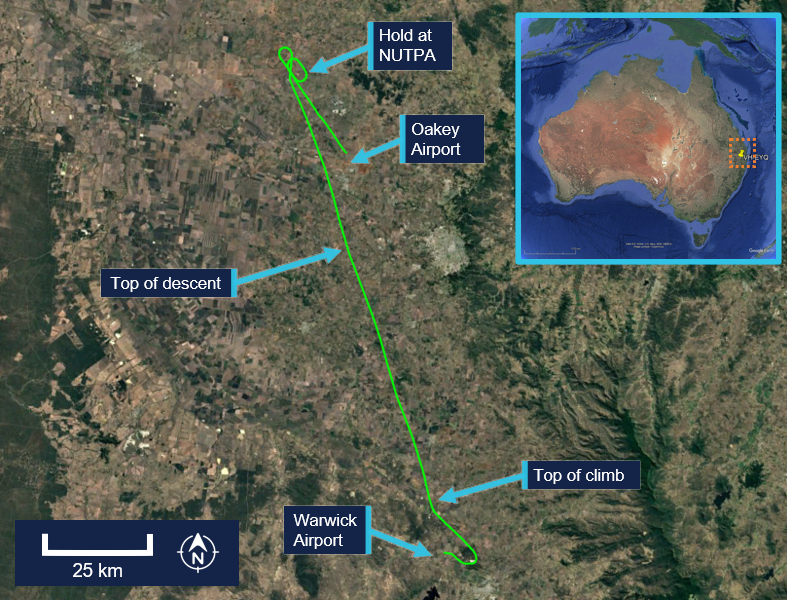
At 1433, Brisbane Centre air traffic control (ATC) issued the pilot with a clearance to track directly to reporting point[3] NUTPA, which was the commencement point for the Oakey Airport runway 14 instrument landing system (ILS)[4] approach (Figure 2).

Figure 2: VH-EYQ flight overview
VH-EYQ flight overview

Source: Google Earth, annotated by the ATSB

At 1439, the pilot advised ATC that they would be conducting airwork in the Oakey area, not above an altitude of 4,000 ft, and they would contact ATC again on completion or by 1530. At that time, the Oakey Airport ATC tower was inactive. After commencing the descent for NUTPA at 1441, the pilot changed frequency to the common traffic advisory frequency (CTAF) in the Oakey Airport area, and all subsequent air-to-air communications took place on the CTAF. Between 1443 and 1454 the pilot made 5 transmissions on this frequency for traffic sequencing purposes. 

At 1450, the aircraft passed overhead NUTPA and conducted one holding pattern. At 1456, the aircraft commenced a descent from 3,800 ft and the pilot made a radio broadcast to advise that the aircraft was established on the ILS. 

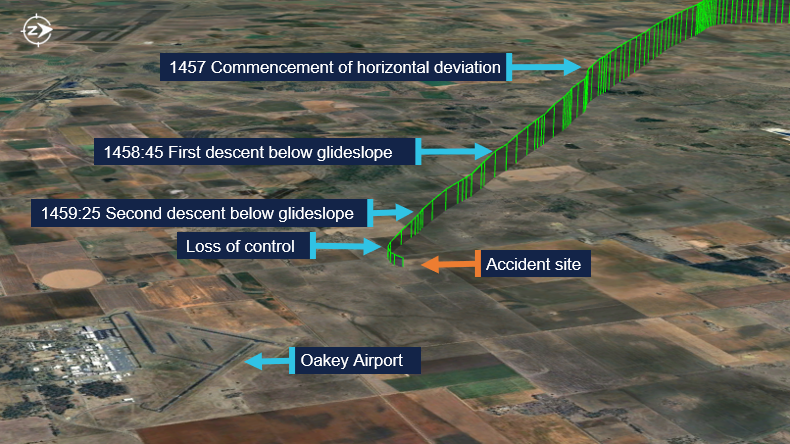
At 1457, the aircraft began to deviate from the horizontal profile for the approach. The aircraft initially deviated right of the extended centreline and then to the left (Figure 3). Fluctuations in vertical speed also occurred during this period. The aircraft continued the approach slightly left of the extended centreline, but the vertical profile of the approach remained on the glideslope.[5] The wind conditions recorded at Oakey Airport at the time were a light breeze of 6 kt, with a mean direction of 190°M (see Meteorological information).

Figure 3: Final approach track
VH-EYQ final approach track


Source: Google Earth, annotated by the ATSB

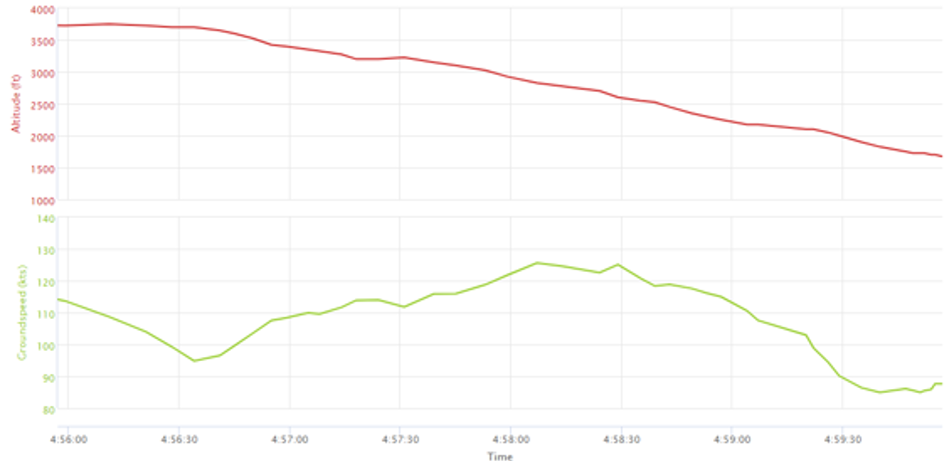
At about 1458:45, and an altitude of 2,500 ft, the aircraft began to descend below the glideslope. This was initially corrected, and the aircraft flew level at about 2,200 ft for 30 seconds. At 1459:25, the aircraft descended below the glideslope again, and the descent continued to an altitude of about 1,700 ft, which equated to a height of between 300–400 ft above ground level (AGL). During this period the aircraft’s groundspeed began to decay. At 1459:39, the aircraft’s groundspeed had reduced to 85 kt (see Recorded flight data). At about 1459:53,[6] a 2‑second radio broadcast was made from the aircraft with an alarm sounding in the background.

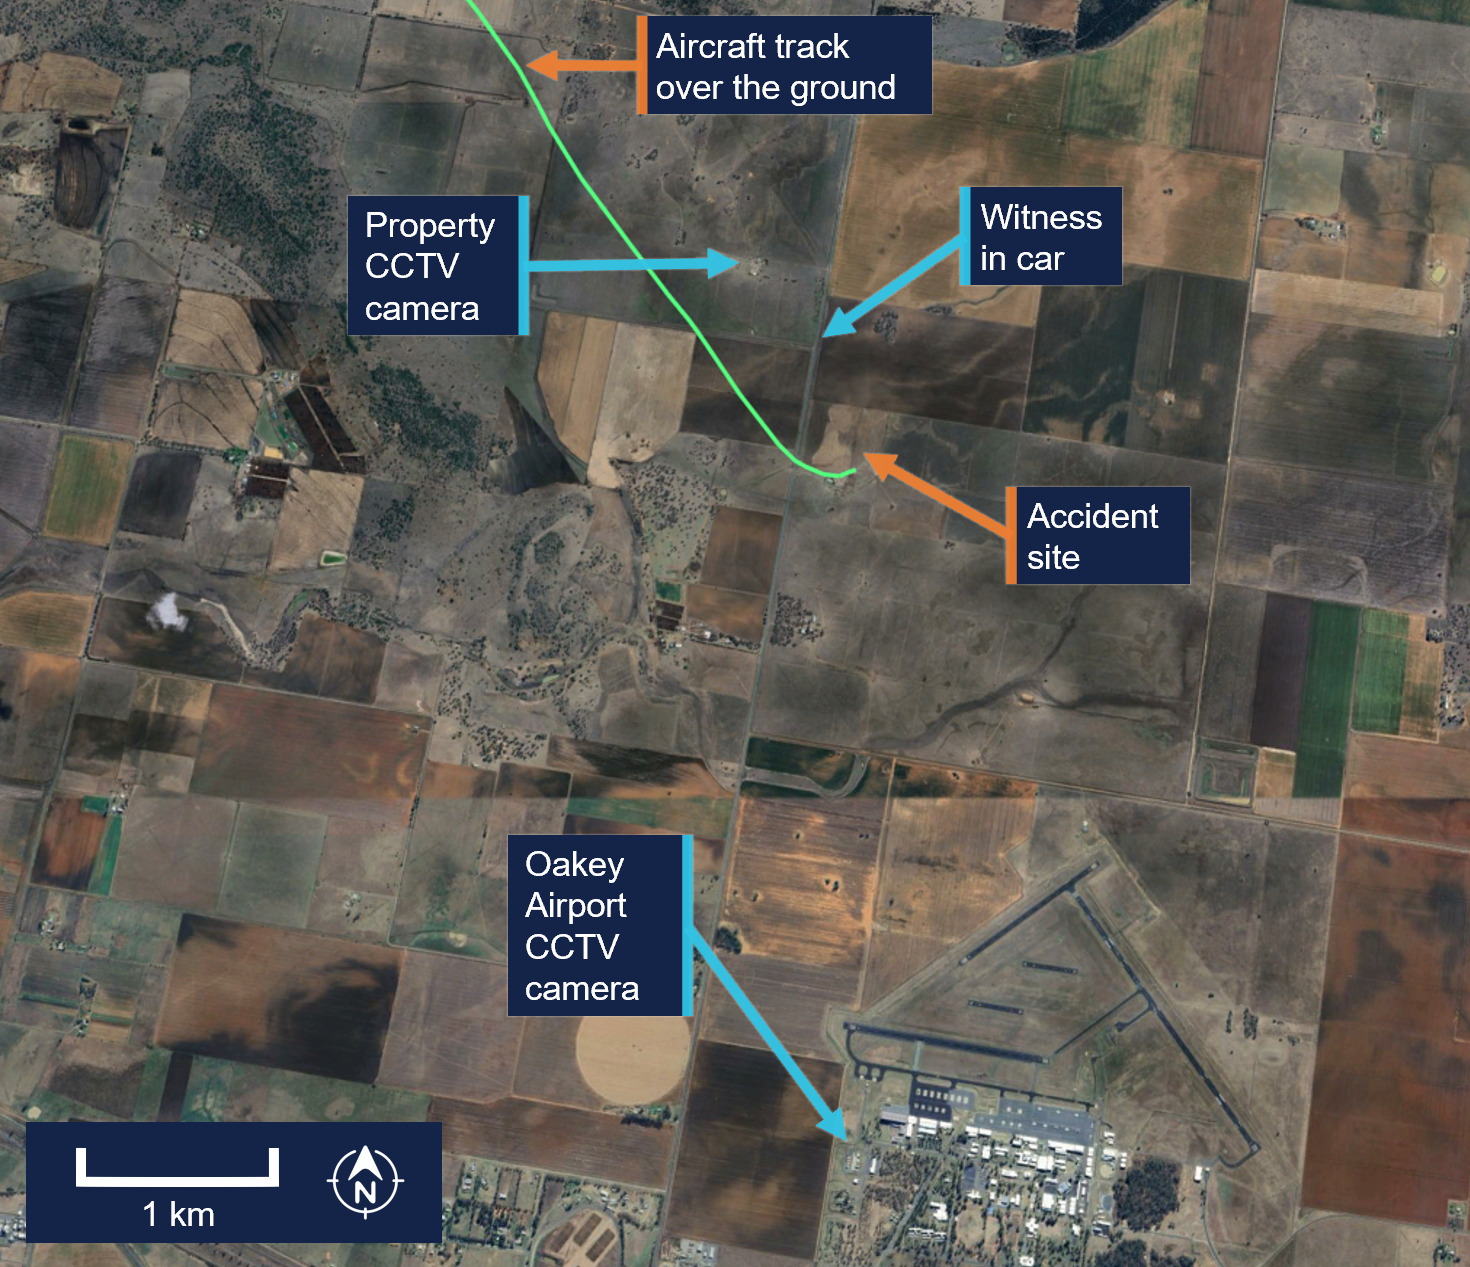
A motorist travelling south observed the aircraft on approach and maintained visual contact with it for about 3 km (Figure 4). They observed the aircraft commence a flat turn and yaw[7] to the left at a height of about 300 ft AGL and pass above the road ahead of them. They recalled seeing the aircraft then roll to the left, pitch down, and impact the terrain. 

Figure 4: Witness and closed-circuit television camera locations
Witness and CCTV camera locations

Source: Google Earth, annotated by the ATSB

Closed-circuit television (CCTV) cameras located at a nearby property and Oakey Airport captured the aircraft commence a steep descent before colliding with terrain (Figure 5).

The aircraft was destroyed in a post-impact fire, and both occupants were fatally injured.

Figure 5: Composite images of recorded CCTV camera footage

Composite images of recorded CCTV camera footage

Source: CCTV camera recordings


Context

Pilot information

Pilot experience

The pilot held a valid class 1 aviation medical certificate and an air transport pilot licence (ATPL) (aeroplane). Additionally, they held a grade 3 flight instructor rating with multi‑engine aeroplane training approval and design feature endorsements to operate VH-EYQ. The pilot held a valid multi-engine instrument rating with the previous instrument proficiency check (IPC) completed in August 2024. 

At the time of the accident, the pilot had accumulated 5,767 hours total aeronautical experience. This included 4,170 flight hours as pilot in command with 3,514 hours in multi-engine aeroplanes and about 1,200 hours in command of a Reims F406. In the preceding 90 days they had flown 95 hours, including 54 hours in the Reims F406. They had worked for the aircraft operator since March 2017.

Known recent activity

The pilot’s work roster for the week prior to the accident (from 14 to 20 July 2025) is shown in Table 1. During this week, the pilot was based away from home and conducted multiple survey flights. The pilot’s duties for 20 July included the survey flight in the morning with no additional rostered flying.

Table 1: Pilot rostered duties, 14 to 20 July 2025

DateShift start-finish timeTotal flight hours
14 JulyOFF0
15 July0630-14301.5
16 July0630-14302.1
17 July0630-14301.8
18 July0630-14302.4
19 JulyOFF0
20 July0730-15005:31

A text message sent from the pilot the evening of 19 July indicated that the pilot had intended to conduct the IPC the following day. Additionally, the message indicated they had sleep opportunity from about 2130. 

Flight examiner information

Flight examiner experience

The flight examiner held a valid class 1 aviation medical certificate and an ATPL (aeroplane). They also held grade 1 flight instructor and flight examiner operational ratings, with multi-engine aeroplane and instrument rating (aeroplane) training approval. Their flight instructor rating also had a spin endorsement, and they held design feature endorsements to operate VH-EYQ. The examiner held a valid multi-engine instrument rating with the previous IPC completed in October 2024.

The flight examiner’s logbook records were destroyed in the post-impact fire. Based on records of the pilot’s hours from January 2025, the flight examiner’s total aeronautical experience was in excess of 20,000 hrs. Additionally, they had flown 3 similar proficiency check flights for the aircraft operator in the previous 12 months, totalling 3.6 hours in the Reims F406. The flight examiner was external to the aircraft operator and was regularly hired to complete the IPC for their pilots.

Known recent activity

Along with their logbook, the flight examiner's work records were destroyed in the post‑impact fire. 

A family member recalled that the flight examiner had returned from a chartered flight to western Queensland on Tuesday 15 July. During the week, they had spent a day providing aviation theory instruction to students but had no other work engagements. On the day of the accident, the flight examiner woke at their normal time. They were reported to have slept well and, when leaving home for the IPC flight, they appeared their normal self with no signs of fatigue.

Aircraft information

General information

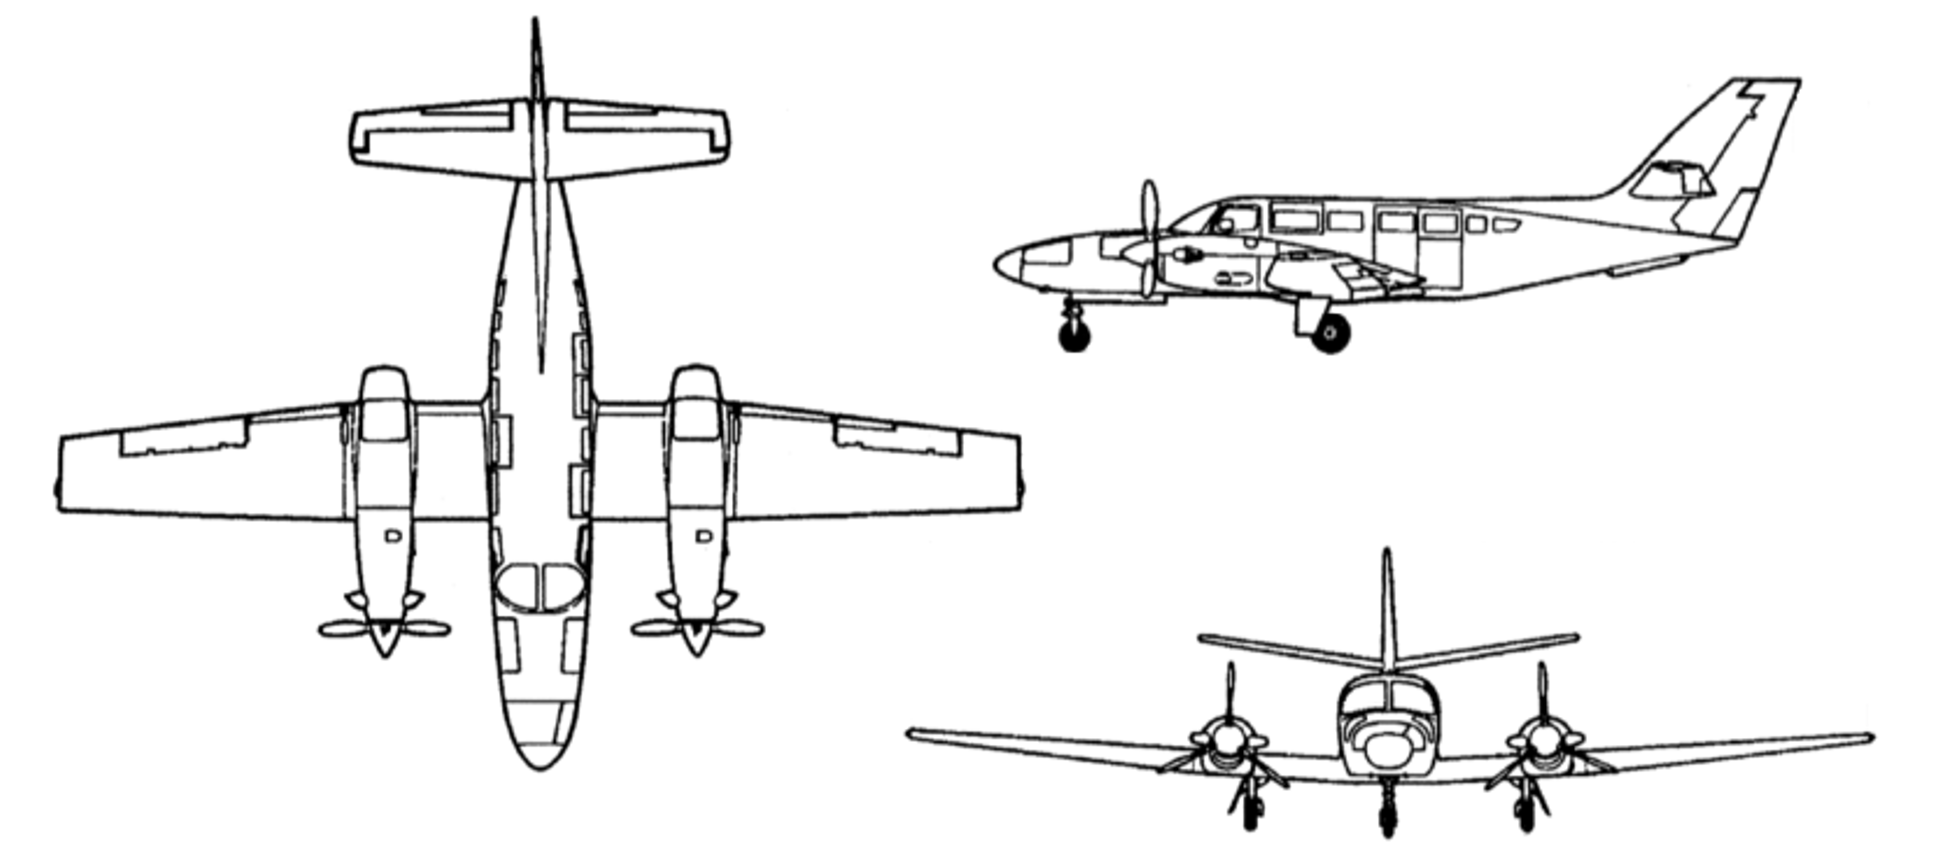
The Reims Aviation F406 is a low wing, twin‑engine aircraft powered by 2 Pratt & Whitney Canada PT6A-112 turbine engines, each driving a 3-bladed McCauley constant speed, full-feathering propeller (Figure 6). The accident aircraft, serial number F406‑0047, was manufactured in France in 1990 and first registered in Australia as VH‑EYQ in 2012. 

Figure 6: Reims F406
Three-view drawing of the Reims F406

Source: ASI Aviation

Recent maintenance activity

The aircraft was to be maintained in accordance with the aircraft operator’s Civil Aviation Safety Authority (CASA) approved system of maintenance. This required a periodic inspection every 100 hours or 12 months, whichever came first. The system of maintenance allowed for periodic inspection intervals to be extended up to a maximum of 10 hours. The most recent periodic inspection was completed on 11 June 2025, at 17,376 hours in service. At the time of the accident, the aircraft had accumulated 17,475.6 hours total time in service.

Configuration

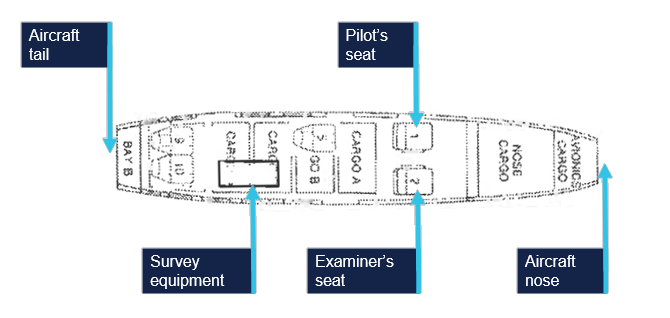
VH-EYQ was configured in a 5-seat survey layout. This comprised the pilot (left) and copilot (right) seats in the front row, followed by 1 passenger seat in row 3, and 2 passenger seats in row 5. The remaining passenger seats were removed from the cabin to accommodate the installation of aerial survey equipment (Figure 7). An electronic loading system had been generated for this configuration by an approved load controller, and records show that this was utilised by the pilot for previous flights.

Figure 7: VH-EYQ cabin configuration
VH-EYQ cabin configuration

Source: ASI Aviation, annotated by the ATSB

Weight and balance

Prior to its departure from Archerfield Airport, the aircraft was fuelled with 1,086 L of Jet A1 fuel. The aircraft operator advised that, based on this fuel uplift and the intended flying activity, it was very likely that the aircraft had full fuel on board for the flight to Warwick Airport. Fuel calculations based on flight times and expected consumption rates indicated that, at the time of the accident, the aircraft probably had about 1,280 L of fuel on board. This meant the aircraft weight at the time of the accident was about 600 kg below the aircraft’s maximum take-off weight. Based on the survey flying configuration and loading of the aircraft, the aircraft’s centre of gravity was calculated and assessed to be within prescribed limits.

Performance

The pilot operating handbook airplane flight manual (POH) provided applicable limitations which included:

  • a stall speed[8] of 75 KIAS[9] in the landing configuration (VSO), and 94 KIAS with flaps in the up position (VS)
  • an intentional one engine inoperative speed (VSSE)[10] of 98 KIAS
  • an air minimum control speed (VMCA)[11] of 90 KIAS
  • a one engine inoperative best rate-of-climb speed at sea level (VYSE) of 108 KIAS. 
One engine inoperative procedures

The POH included recommended procedures in the event of an emergency. This included checklists for an engine failure in flight, and for the conduct of an approach and missed approach with one engine inoperative. The recommended approach speed with an engine inoperative was 110 KIAS reducing to 101 KIAS only once landing was assured.

Site and wreckage information

Accident site

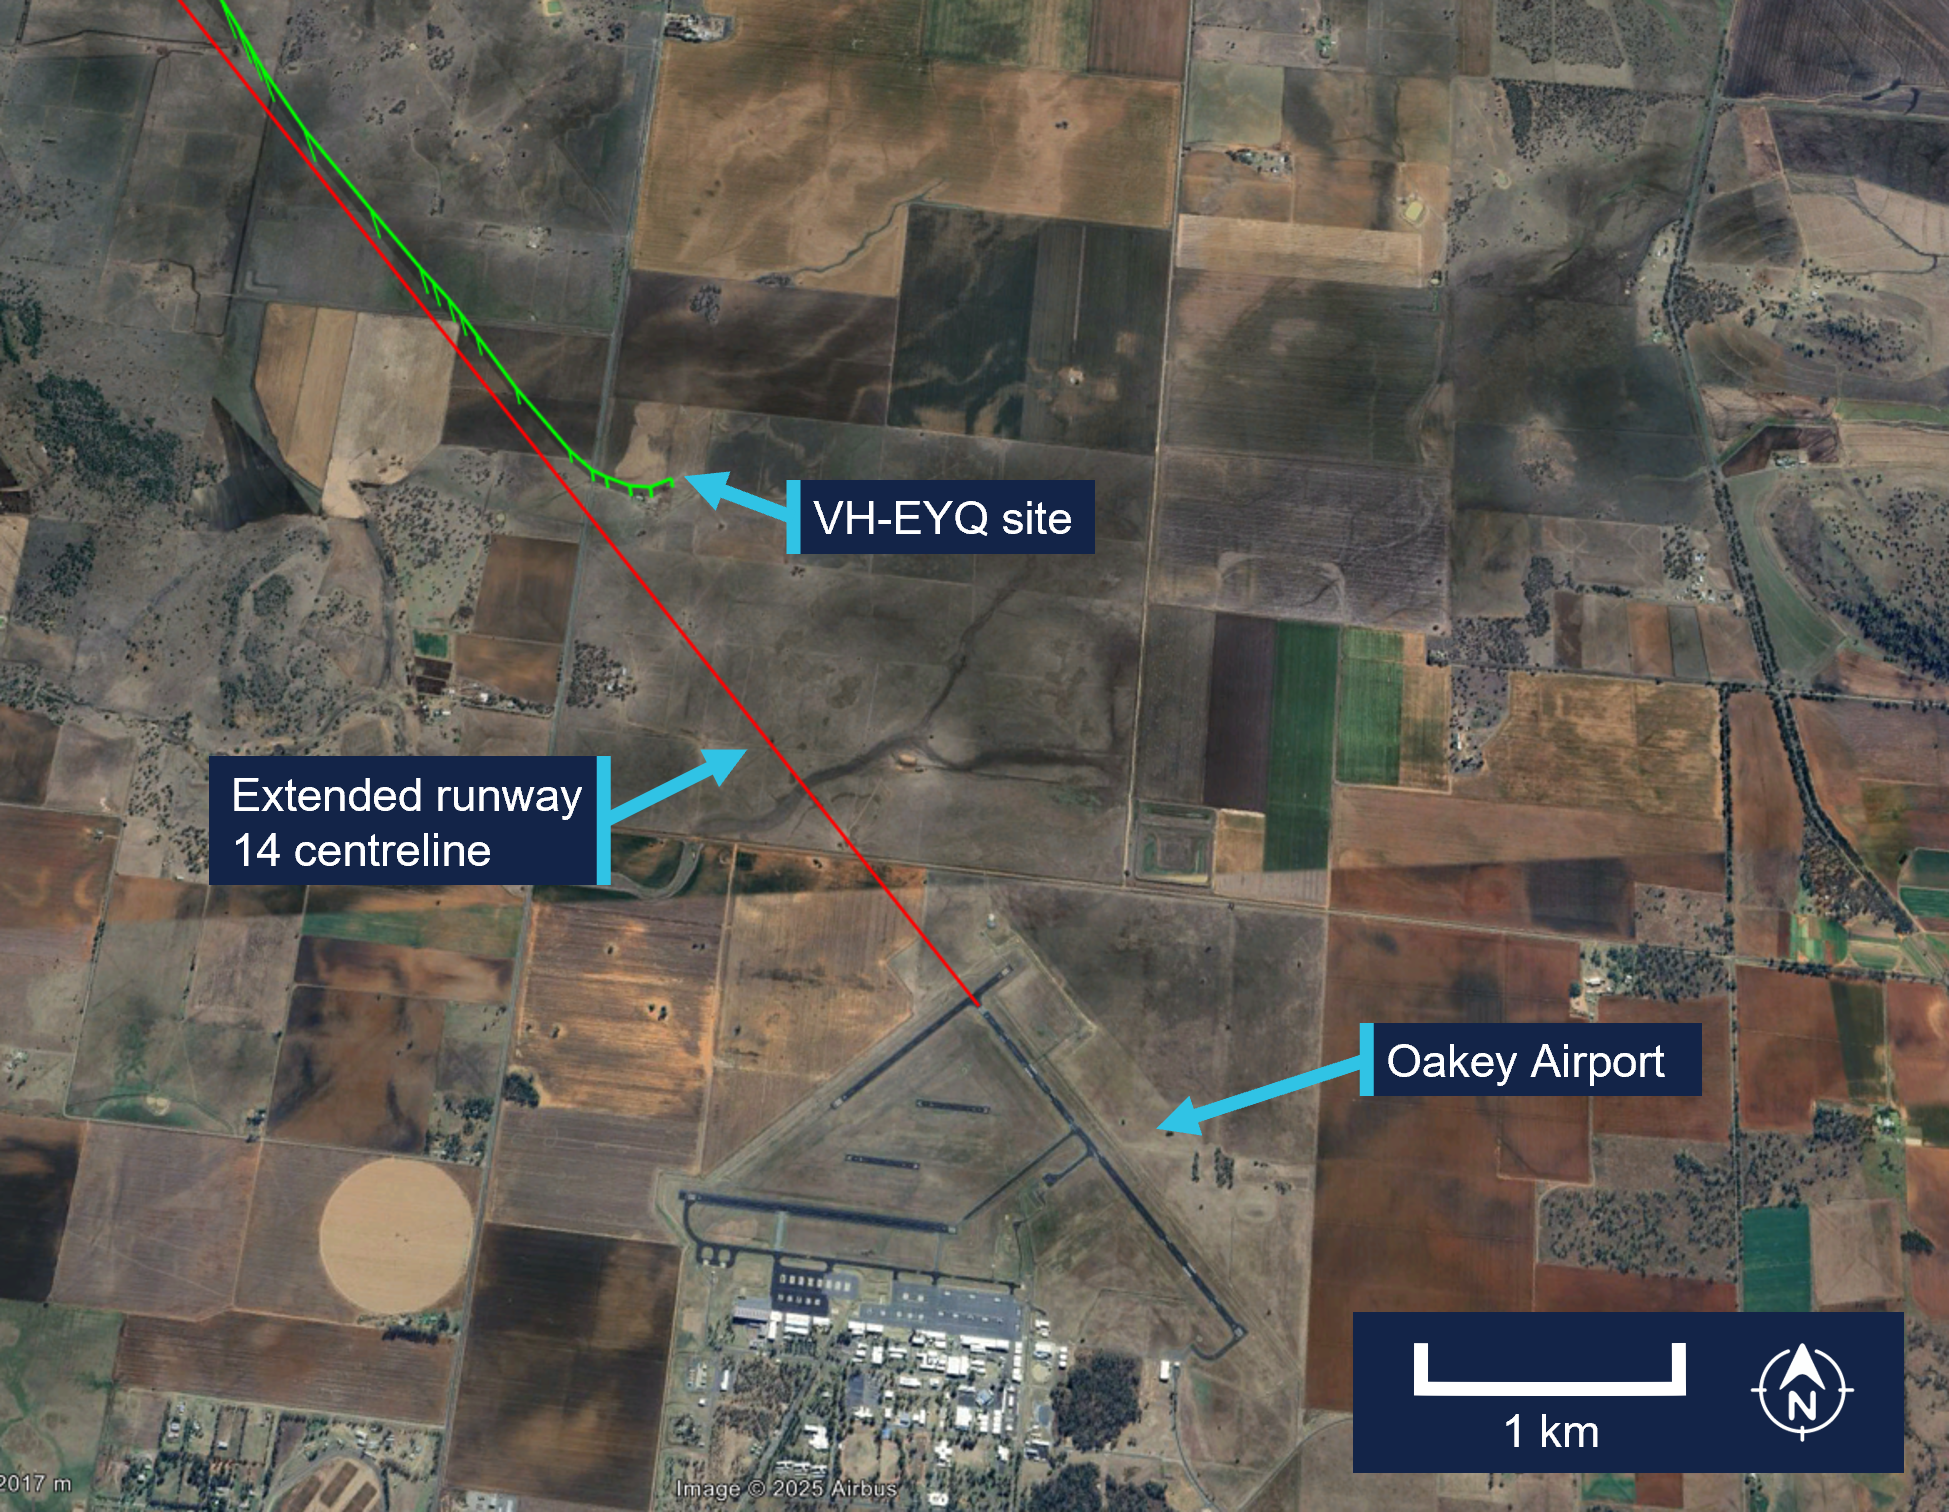
The ATSB conducted an onsite examination of the aircraft wreckage, which was located in an open paddock about 2.6 km from the threshold of runway 14 at Oakey Airport (Figure 8).

Figure 8: Location of accident
Location of accident

Source: Google Earth, annotated by the ATSB

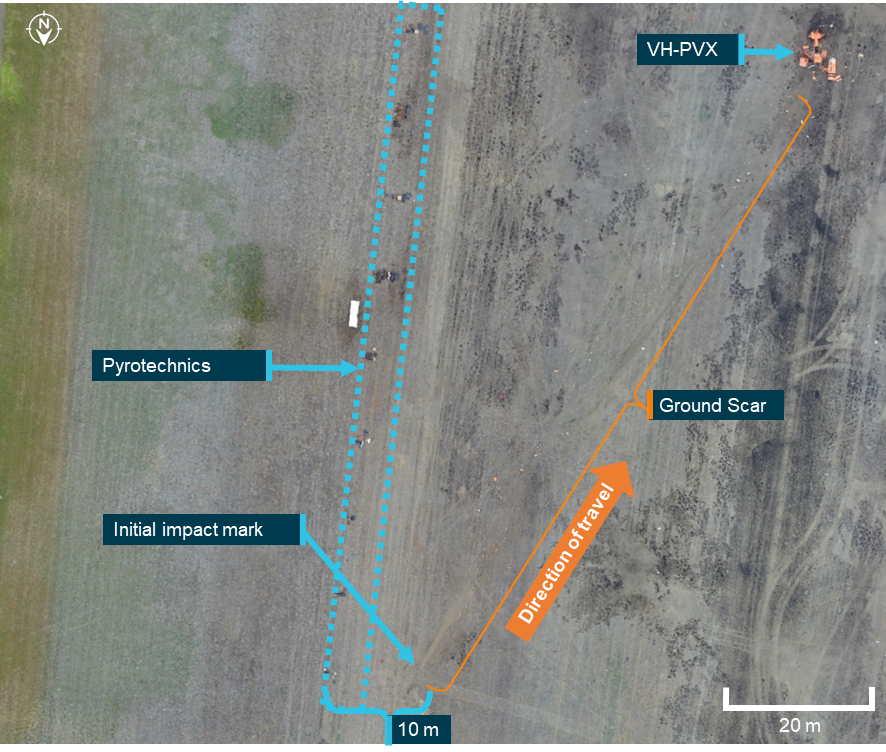
The wreckage was confined to a 30 m radius of the accident site. The impact marks and wreckage position indicated the aircraft impacted terrain left wing low with little forward momentum. Ground scars indicated the aircraft moved about 6 m after the initial impact. All components were upright.

The tail and aft cabin section showed signs of vertical compression. There was no fore or aft compression damage to the nose or wings. The left wing had separated from the aircraft just outboard of the left engine, and the right wing had separated just inboard of the right engine. Both wings had swung forward to lay parallel to the fuselage (Figure 9).

Figure 9: VH-EYQ accident site

VH-EYQ accident site

Source: ATSB

All major aircraft components were accounted for at the point of impact. A post‑impact fire consumed the forward section of the aircraft to the aft cabin door (Figure 10). This damage limited the extent to which pre-impact defects could be identified.

Figure 10: VH-EYQ wreckage

VH-EYQ wreckage

Source: ATSB 

Engines

Both engines were retained for further examination. This was conducted by ATSB investigators who were assisted by investigators from Pratt & Whitney Canada.[12] The engine examination determined: 

  • there were no indications of pre-impact mechanical anomalies to any of the engine components that would have precluded normal engine operation
  • the left engine displayed indications that it was rotating at the time of impact
  • the right engine displayed characteristics that it was developing power at the time of impact.
Propellers

Both propellers showed indications that the engines were running at impact. The right propeller was determined to be in a fine pitch position[13] and exhibited bending in multiple directions.

Both propellers were retained, and an independent inspection was carried out at a propeller overhaul facility under the direction of ATSB investigators. Further analysis is required to determine the position of the left propeller at the time of impact.  

Meteorological information

The Bureau of Meteorology (BoM) graphical area forecast valid at the time of the accident included the following conditions en route:

  • scattered cloud bases of 3,000 ft to 5,000 ft, extending up to 8,000 ft
  • isolated showers of rain with broken cloud from 1,000 ft to 2,000 ft and scattered cloud from 2,000 ft to above 10,000 ft.

At 1500, at about the same time the aircraft impacted terrain, the BoM issued a meteorological aerodrome report for Oakey Airport which reported the conditions at that time were:

  • a wind of 6 kt, with a mean direction of 190°M, varying between 160°M–220°M
  • visibility of 10 km or greater
  • no cloud detected
  • a temperature of 20°C and a dew point of 6°C
  • a QNH[14] of 1,016 millibars
  • no recorded rainfall since 0900.

Satellite images and CCTV footage captured areas of scattered cloud in the vicinity of the aerodrome at the time of the approach.

Flight activity

General

For a pilot to operate an aircraft under the instrument flight rules, they are required to hold an instrument rating. Pilots are also required to pass an annual instrument proficiency check (IPC) flight to ensure that they maintain the necessary skills and competency to operate safely. The purpose of the accident flight was for the pilot to complete their annual IPC. 

An IPC can be completed by a flight examiner with an instrument rating, MPL[15] or ATPL (aeroplane) flight test endorsement, or by a person approved by CASA. While the aircraft operator had a training and checking system,[16] they scheduled IPC flights with external examiners and permitted the pilots to arrange their IPC flights privately. The head of flying operations (HOFO) of the aircraft operator recalled that the accident pilot had advised them that their IPC expiry date was approaching and requested the use of VH‑EYQ to complete the flight. In response, provisions were made by the HOFO and head of aircraft airworthiness and maintenance control delegate to make the aircraft available to the pilot for the purpose of conducting the IPC flight. 

The pilot arranged the IPC with the external flight examiner and records show that the IPC was booked into the CASA flight test management system[17] by the flight examiner during the afternoon of 18 July and scheduled to take place on the afternoon of 20 July. 

Instrument proficiency check assessment

During an IPC flight, a pilot’s competency is assessed in actual or simulated instrument meteorological conditions. During the flight, a pilot is required to meet specified standards for:

  • departure
  • en route skills
  • arrival
  • approach
  • missed approach
  • approach to land manoeuvres.

If the IPC is for multi-engine operations, the assessment also requires the satisfactory completion of a simulated one engine inoperative (OEI) departure and a simulated OEI approach. 

The HOFO of the aircraft operator recalled that the external flight examiner had, in the past, typically conducted the simulated OEI departure after take-off from Warwick Airport and the simulated OEI approach at Oakey Airport. 

Recorded information

Recorded flight data

The aircraft was not fitted with a flight data recorder or a cockpit voice recorder, nor was it required to be. During the accident flight, data was being transmitted by the aircraft’s automatic dependent surveillance broadcast (ADS-B) equipment. This data, recorded at 2–5 second intervals by amateur ground-based receivers, captured the aircraft’s position, altitude and groundspeed during the flight. Flight data was also being transmitted from a Spidertracks[18] tracking device fitted to the aircraft. This data, recorded at 15-second intervals, captured the aircraft’s position, altitude, groundspeed and heading during the flight.

The ADS-B altitude and groundspeed data for the aircraft’s departure from Warwick Airport is depicted in Figure 11.

Figure 11: VH-EYQ altitude and groundspeed during the Warwick Airport departure
AO-2025-042 prelim Figure 11.png

Source: ATSB 

The ADS-B altitude and groundspeed data for the aircraft’s ILS approach at Oakey Airport is depicted in Figure 12.

Figure 12: VH-EYQ altitude and groundspeed during the Oakey Airport approach
VH-EYQ altitude and groundspeed during the Oakey Airport approach

Source: ATSB 

A Garmin GTN-650 global positioning system was also recovered from the accident site and transported to the ATSB’s Canberra technical facility for further examination. The unit showed signs of significant heat damage with melting and evidence of charring on the internal circuitry. The remains of 2 SD[19] cards were found within the unit, however, the post-impact fire had damaged the SD card memory chips to the point that data could not be extracted using normal recovery methods. 

Record radio communications

All radio communications made and received by Airservices Australia throughout the entirety of VH-EYQ’s flight from Warwick Airport were recorded.

Recorded CCTV footage

Two CCTV cameras captured footage of the aircraft immediately prior to the collision with terrain. One camera was located on a property 1.4 km to the north-west of the accident and the second camera was located on Oakey Airport about 3 km south of the accident site. 

The property CCTV footage was timestamped. The aircraft entered frame at 1459:53 and remained in frame for the duration of the recording which captured the collision with terrain at 1500:00.

The Oakey Airport CCTV footage did not contain a timestamp. The aircraft entered frame 1 second into the recording and remained in frame until the collision with terrain that occurred 7 seconds later.

Further investigation

To date, the ATSB has:

  • examined the wreckage and accident site
  • examined meteorological information
  • interviewed relevant parties
  • collected radio communication, aircraft traffic surveillance data, and navigational application data
  • collected aircraft, pilot, crew and operator documentation.

The investigation is continuing and will include review and examination of:

  • pilots’ recent history
  • propellers
  • maintenance records
  • pilot and crew training and medical records
  • operational procedures and documentation
  • further interviews with relevant parties
  • flight data and air traffic surveillance data
  • the requirements of conducting simulated one engine inoperative exercises at low heights.

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken. 

Acknowledgements

The ATSB would like to acknowledge the assistance provided by the Australian Defence Force personnel at the Oakey Army Aviation Centre during the initial evidence collection activities.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Instrument proficiency check: an assessment of a pilot’s skills and operational knowledge required to exercise licence ratings and privileges when flying under the instrument flight rules.

[2]     Instrument flight rules (IFR): a set of regulations that permit the pilot to operate an aircraft in instrument meteorological conditions (IMC), which have much lower weather minimums than visual flight rules (VFR).

[3]     Reporting point: a specified geographical location in relation to which the position of an aircraft can be reported.

[4]     Instrument landing system (ILS): a precision instrument approach system which normally consists of a VHF localiser providing horizontal guidance and a UHF glideslope providing vertical guidance.

[5]     Glideslope: a component of the instrument landing system providing vertical (up/down) guidance toward the runway touchdown point, usually at a 3° slope.

[6]     The provided CTAF recording was found to have a discrepancy that could not be resolved.

[7]     Yaw: the motion of an aircraft about its vertical or normal axis.

[8]     Aerodynamic stall: or stall, occurs when airflow separates from the wing’s upper surface and becomes turbulent. A stall occurs at high angles of attack, typically 16˚ to 18˚, and results in reduced lift.

[9]     KIAS: indicated airspeed expressed in knots, used by pilots as a reference for all aircraft manoeuvres.

[10]    The manufacturer’s minimum speed for rendering one engine inoperative in flight for pilot training.

[11]    The minimum indicated airspeed at which the aircraft was laterally controllable with one engine inoperative and a 5° bank angle towards the operative engine.

[12]    Pratt & Whitney Canada: engine manufacturer of the engines installed on VH-EYQ.

[13]    Fine pitch: refers to a fine or low pitch angle which yields good low speed acceleration.

[14]    QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean seal level.

[15]    MPL: multi-crew pilot licence.

[16]    Training and checking system: a training and checking system ensures that operational safety-critical personnel are proficient in the required competencies to support an operator's air operations.

[17]    Flight test management system: online record system used to notify CASA of planned flight tests. Flight examiners also use the system to schedule and record the outcomes of flight tests and proficiency checks. The system is used by CASA to keep track of the flight testing process and analyse trends at industry level.

[18]    Spidertracks: a satellite-based tracking system, combining satellite communication and GPS technology.

[19]    Secure digital card (SD): a type of memory card typically used in portable devices.

Occurrence summary

Investigation number AO-2025-042
Occurrence date 20/07/2025
Occurrence time and timezone 15:00 Australian Eastern Standard Time
Location 3.4 km north of Oakey Airport
State Queensland
Report release date 10/12/2025
Report status Preliminary
Anticipated completion Q4 2026
Investigation level Short
Investigation type Occurrence Investigation
Investigation phase Examination and analysis
Investigation status Active
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Loss of control
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Reims Aviation S.A.
Model F406
Registration VH-EYQ
Serial number F406-0047
Aircraft operator Bayswater Road Pty Ltd (trading as Aero Logistics)
Sector Turboprop
Operation type Part 91 General operating and flight rules
Activity General aviation / Recreational-Instructional flying-Instructional flying - dual
Departure point Warwick Airport, Queensland
Destination Warwick Airport, Queensland
Injuries Crew - 2 (fatal)
Damage Destroyed

Collision with terrain involving Eurocopter EC120B, VH-JDZ, Porepunkah Aerodrome, Victoria, on 15 May 2025

Final report

Report release date: 06/11/2025

Investigation summary

What happened

On 15 May 2025, a Eurocopter EC120B helicopter, registered VH-JDZ, was operated at Porepunkah aerodrome, with a pilot and one passenger on board. While lifting into a hover, left yaw was allowed to develop without correction. After turning 180° the pilot attempted to arrest the yaw with right pedal input. However, the yaw continued and the helicopter began to rotate, entering an uncontrolled turn. After about three quarters of a revolution the right skid contacted the ground while the helicopter continued to rotate. The helicopter then rolled over, resulting in substantial damage to the aircraft. Neither the pilot nor the passenger sustained injury and safely exited the aircraft.

What the ATSB found

Adequate control of the left yaw after hover was not achieved due to the insufficient application of opposing right pedal input to the tail rotor. 

The pilot was highly experienced in rotary wing operations, though reported that they had not flown this type of helicopter (EC120B) for about 15 years. The EC120B is fitted with a Fenestron tail rotor which requires greater pedal response than conventional tail rotor helicopters to counter the torque effect. In this case the pilot had more recent experience flying helicopters with a conventional tail rotor system. Although they were a highly experienced helicopter pilot, the limited recent type-specific experience on the EC120B had degraded their ability to respond appropriately to the helicopter’s different pedal requirements.

Safety message

Maintaining recent type-specific flight experience is vital to prevent degraded performance when transitioning between aircraft with differing control characteristics. 

Understanding the aircraft’s characteristics is important for helicopter pilots so that they can anticipate its response when becoming airborne and are not surprised by events. Controlling yaw in helicopters with a Fenestron tail rotor, as in this case, is an essential consideration. Airbus Helicopters and the European Union Aviation Safety Agency (EASA) provide specific guidance relating to this issue to assist pilots.


The investigation

The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 15 May 2025, a Eurocopter[1] (Airbus Helicopters) EC120B helicopter, registered VH‑JDZ, was operated at Porepunkah aerodrome, Victoria, for planned private flight to Albury, about 38 NM to the north. On board were the pilot and a passenger, who was also licenced and qualified on the helicopter. 

On arrival at the aerodrome, the pilot and passenger prepared the helicopter by moving it out of the hangar and conducting a visual inspection in preparation for flight. At about 1300, the pilot commenced engine start and a short time later began the take-off sequence and brought the helicopter into a hover. The pilot reported that the helicopter was initially slow to lift off but then rapidly rose and began an uncommanded 90° left yaw.[2] The pilot stated that although the yaw was not commanded, they intended to turn in that direction anyway so allowed the yaw to continue and planned to arrest it after it turned 180°. 

The pilot then attempted to correct the left yaw with right pedal input while simultaneously pulling up the collective to gain more height. However, the yaw was not adequately countered and with additional torque, the left yaw increased. The helicopter then began to rotate and entered an uncontrolled turn. 

The pilot was unable to regain control and the helicopter completed about three quarters of a revolution before the right aft skid contacted the ground, leading to a further rotation on the ground and a dynamic rollover.[3]

The helicopter came to a rest on its right side and the pilot immediatley checked on the welfare of the passenger and turned off the fuel. Noticing smoke and mindful of the potential fire risk, the pilot gave instructions to evacuate immediately. 

With some difficulty, due to their wreckage position, both occupants removed their seat restraints, independently exited the helicopter and moved to an area a safe distance away from the wreckage. 

As a result of the impact, the aircraft was substantially damaged (Figure 1).

Aerodrome staff and an ambulance arrived at the site shortly after the incident and conducted a medical assessment. It was determined that neither occupant had sustained serious injury. 

Figure 1: VH-JDZ photographed after the dynamic rollover 

Photograph of the damaged helicopter wreckage after dynamic rollover.

Source: Owner

Context

Pilot information 

The pilot held a commercial pilot licence (CPL-H) helicopter issued in September 1994. At the time of the occurrence the pilot’s total flying experience was 11,257 flight hours and they were endorsed to fly the EC120B and had previously owned and operated a commercial helicopter business.

In the 12 months before the accident, the pilot had logged about 100 flight hours, primarily in a Robinson R44. They stated they had not flown an EC120B for about 15 years. 

The pilot held a Class 1 aviation medical certificate and reported having a regular sleep pattern of about 7.5–8 hours nightly and had no feeling of fatigue on the day of the incident.

To exercise the privileges of a flight crew licence, the regulations require the pilot to have a valid helicopter flight review (HFR). The pilot last completed this on 6 October 2024 in a Robinson R44 while obtaining a low-level endorsement on the same date.

Aircraft information 

The EC120B is a 5-seat, light utility helicopter, powered by a single turboshaft engine. It has a 3-blade main rotor head and a Fenestron anti-torque tail rotor (see Fenestron tail rotor).

The EC120B is powered by a Safran Helicopter engines Arrius 2F single gas turbine engine. VH-JDZ was manufactured in France in 2003 and was first registered in Australia on 24 June 2003. The current owner purchased the helicopter on 14 September 2021. 

The helicopter’s maintenance release showed the last daily inspection was completed on 2 May 2025 and showed the helicopter had accrued about 3,172 hours flight time.

Fuel, weight and balance 

The pilot reported that the helicopter was carrying a full fuel load. The maximum take of weight (MTOW) is 1,715 kg, of which the fuel capacity is about 410 litres (326 kg) of aviation turbine fuel. With the pilot and passenger on board and full fuel tanks, the helicopter weighed about 1,560 kg which was below the MTOW and within balance. 

Flight controls

The helicopter was fitted with standard primary flight controls: cyclic,[4] collective[5] and dual tail rotor anti-torque pedals. The pilot stated that the passenger (also a rated pilot) did not touch the controls. The aircraft was equipped with a single hydraulic system, which assisted main rotor control through 3 hydraulic servos. The tail rotor was not hydraulically assisted and dual controls were installed in the helicopter which are removable when not required. The pilot reported that they were not removed but had adjusted the pedals prior to flight on their side to suit their leg length.

Aircraft handling characteristics
Fenestron tail rotor

The EC120B is equipped with a Fenestron tail rotor or fan-in-fin system (Figure 2). The vertical fin or stabiliser was designed to provide aerodynamic directional stability in forward flight and is larger than those found on similar-sized helicopters with a conventional tail rotor (CTR). The fin was paired with a 0.75 m diameter, 8-bladed tail rotor. The tail rotor was mounted on stators[6] integrated into the vertical fin. 

These features combined to change the aerodynamics of the tail rotor, and the relative effectiveness of the anti-torque pedals for a given range of movement, when compared with helicopters with a CTR. Because the tail rotor blades are located within a circular duct, the Fenestron design is considered a safety feature, reducing the risk of contact with people or objects. 

Figure 2: Illustration of the design difference between the Fenestron tail rotor and a conventional tail rotor

Photo of a conventional tail rotor and a Fenestron tail pictured side by side.

Source: ATSB

Anti-torque pedals 

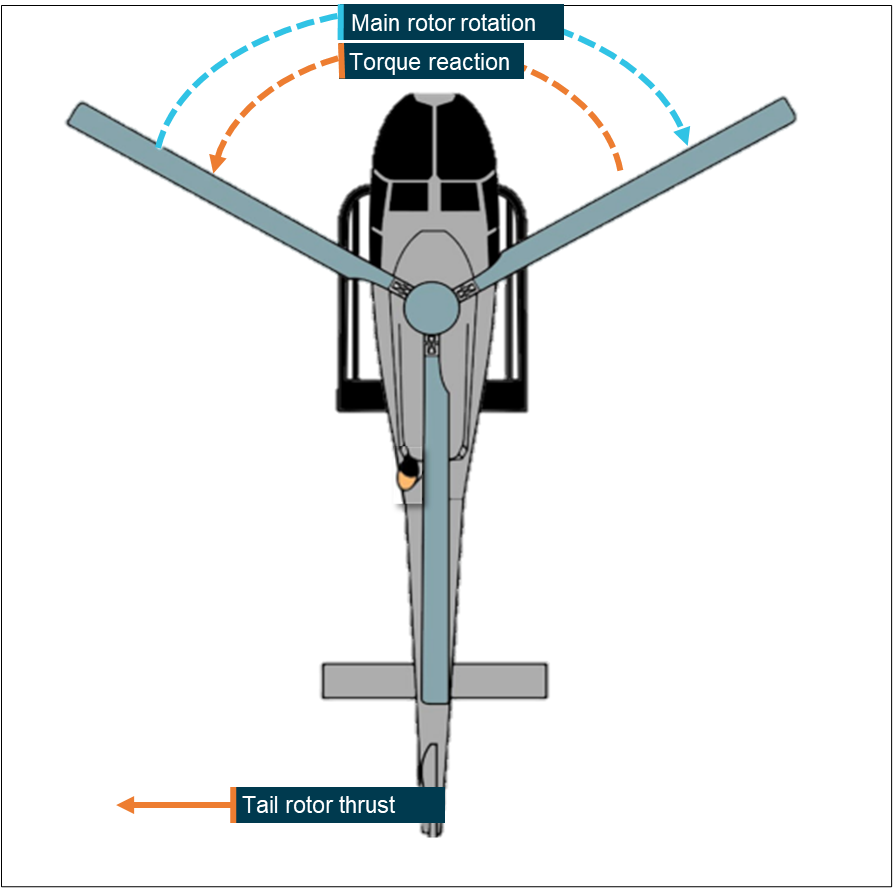
The main rotor on the EC120B rotated clockwise (as viewed from above). The main rotor is driven from a central point, resulting in a torque reaction which causes the fuselage of the helicopter to yaw in the opposite direction to the main rotor’s rotation (Figure 3). In the case of the EC120B, this torque reaction means the helicopter will yaw to the left when power is applied. The force to resist and balance the yaw is produced by the tail rotor and is controlled by the anti-torque pedals in the cockpit. Tail rotor thrust can be increased by pushing the right anti-torque pedal to force the nose to yaw to the right. When a pilot demands power from the engine to increase lift, or as a result of lifting the collective (increasing main rotor blade angle), the torque reaction and yaw to the left will increase. 

While both types of helicopters (Fenestron and CTR) may have the same methods of handling unanticipated yaw, the direction of rotation means that opposite pedal inputs are required and there are different requirements for the magnitude of pedal input and different expected performance (Airbus, 2020). 

Figure 3: Direction of main rotor rotation for the EC120B showing corresponding torque reaction

Image that shows the direction of main rotor rotation for the EC120B showing corresponding torque reaction.

Source: ATSB

Manufacturer’s guidance on unanticipated yaw 

Unanticipated yaw at low speed has previously been the subject of Safety Information Notices (SIN) published by Airbus Helicopters. In 2005, Eurocopter (prior to becoming part of the Airbus group) released Service Letter 1673-67-04 (Reminder concerning the YAW axis control for all helicopters in some situations). The service letter reminded pilots that Fenestron tail rotors required significantly more pedal travel than conventional tail rotors when transitioning from forward flight to a hover. 

Airbus Helicopters issued SIN 3297-S-00 Unanticipated left yaw (main rotor rotating clockwise), commonly referred to as LTE[7] in 2019. This notice outlined a detailed explanation of the phenomenon of unanticipated yaw due to insufficient pedal application. The full notice is provided in SIN 3297-S-00 and details of some related accidents are provided in Appendix A of ATSB report AO-2018-026. 

The Airbus notice defined unanticipated yaw as an ‘uncommanded rapid yaw rate which does not subside of its own accord’. The notice also stated: 

Unanticipated yaw is a flight characteristic to which all types of single rotor helicopter (regardless of anti-torque design) can be susceptible at low speed, often dependent on the direction and strength of the wind relative to the helicopter… 

…Where this type of unanticipated yaw situation is encountered, it may be rapid and most often will be in the opposite direction of the rotation of the main rotor blades (i.e. left yaw where the blades rotate clockwise). Swift corrective action is needed in response otherwise loss of control and possible accident may result. 

However, use of the rudder pedal in the first instance may not cause the yaw to immediately subside, thus causing the pilot to make inadequate use of the pedal to correct the situation because he suspects that it is ineffective when, in fact, thrust capability of the tail rotor available to him remains undiminished. "Loss of tail rotor effectiveness" is not, therefore, a most efficient description as it wrongly implies that tail rotor efficiency is reduced in certain conditions.

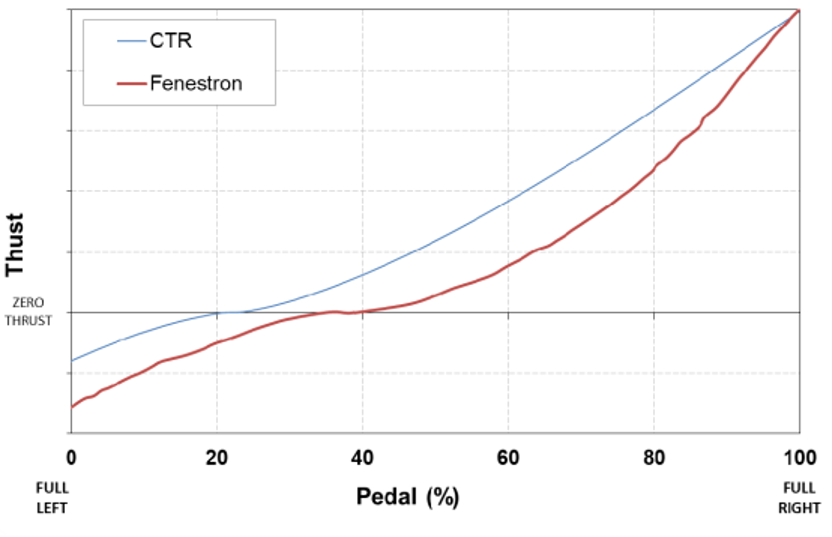
Related to SIN 3297-S-00 and superseding Service Letter 1673-67-04, Airbus issued SIN 3539-I-00 in 2020 (Fenestron versus Conventional Tail Rotor for helicopters equipped with a main rotor rotating clockwise when seen from above). This notice identified some specific characteristics of the Fenestron design, especially when transitioning from a helicopter equipped with a CTR. SIN 3529-I-00 showed graphically how the thrust varies with the pedal position on a Fenestron and on a CTR in hover conditions (Figure 4). The notice stated:

More negative thrust is required at 0% pedal position with a Fenestron to counterbalance the larger fin lateral lift in autorotation. The change of slope in the vicinity of zero thrust is more pronounced on the Fenestron curve than on the CTR curve. The CTR curve is more linear. The effect of a control input is almost constant in the whole pedal range, while it significantly varies for the Fenestron. The slope, and thus the perceived efficiency of the control, is much larger when coming close to full right pedal stop.

Figure 4: Comparison of Fenestron and conventional tail rotor in hover

A graph with a line showing the difference in pedal and thrust for a conventional helicopter tail rotor and a fenestron tail

Source: Airbus Helicopters

The pilot stated they were not aware of the information provided by Airbus, but were aware of the increased pedal input required to achieve tail rotor authority due to their previous flying experience on type.

Meteorological conditions 

Meteorological conditions were not recorded at Porepunkah aerodrome, however during interview, the pilot and the passenger reported that no adverse weather conditions had been forecast or were observed. The pilot identified that there was very little wind directly before the incident as indicated by the windsock at the aerodrome. They estimated the wind to be very light as the pilot reported the windsock appeared to be wrapped around the flagpole.

General competency requirements

The Civil Aviation Safety Authority (CASA) recognises that skill decay occurs over time, and that checks are an ongoing measure and ensure that the licence competencies specified in the Civil Aviation Safety Regulation (CASR) Part 61 Manual of Standards continue to be met. 

HFR is an opportunity for pilots to practise in-flight emergencies with an instructor and to demonstrate the required competence to safely operate a helicopter every 2 years. In discussing the aim of a flight review, CASA published Civil Aviation Advisory Publication (CAAP) 5.81-01 - Flight crew licensing flight reviews, which stated: 

...With the passage of time and lack of practice some skills and knowledge can degrade. A flight review affords the opportunity to restore these degraded skills and gain new knowledge. 

The flight review must be seen in the context of a broader aviation safety philosophy. The flight review, although important (and required by legislation), is one process that contributes to continuing pilot proficiency and consequently the safety of flight. A flight review every two years does not, in itself, ensure safety. Safety is achieved when each pilot takes responsibility for a continuing process of hazard identification and risk management for their own aviation activities. 

CASR Part 61.385 Limitations on exercise of privileges of pilots licences – general competency requirement states:

 - The holder of a pilot licence is authorised to exercise the privileges of the licence in an aircraft only if the holder is competent in operating the aircraft to the standards mentioned in the Part 61 Manual of Standards for the class or type to which the aircraft belongs… 

CASA recommends that pilots should refresh their knowledge before commencing their next flight. 

The guidance acknowledges that while a flight review can restore degraded skills it should be seen within the broader context of aviation safety. Regulations alone cannot guarantee safe outcomes and do not remove the need for pilots to monitor and maintain their own level of competency before flying.

Skill decay

Skill decay, sometimes termed as skill fade, is a recognised phenomenon in aviation particularly when pilots have not flown a specific aircraft type for some time. Arthur and others (1998) defined skill decay as ‘the loss or decay of trained or acquired skills (or knowledge) after periods of non-use’. Wang and others (2013) note several factors that influence skill decay such as retention interval, task type, conditions of retrieval, training methods, individual ability. 

Skill decay is particularly salient in situations where individuals receive training on information and skills that they may not be required to use for extended periods of time. Previous research identified that there is a negative relation between skill retention and the length of non-use, starting from the day of training, with participants showing a 92 per cent reduction in performance when more than 365 days elapse between training and performing the skill again (Arthur and others 1998)

The pilot had logged nearly 12,000 hours on rotary aircraft but had not piloted an EC120B for over a decade. 

Related occurrences

There have been a considerable number of accidents resulting from unanticipated yaw in helicopters at low height and low airspeed, both nationally and internationally. This is illustrated in the following cases drawn from other investigation reports.

Accident involving EC130 at Mansfield, Victoria, on 19 January 2019

The helicopter rolled on its side during take-off, resulting in substantial damage to the helicopter and minor injuries to the pilot. The ATSB report 

AO-2019-005 (355.44 KB)

stated:

On the morning of 19 January 2019, a Eurocopter EC130 helicopter, registered VH-YHS, conducted a private flight from Moorabbin Airport to an authorised landing area (ALA) near Mansfield, Victoria with the pilot and two passengers on board. A return flight to Moorabbin was planned for later that afternoon. At about 1500… the pilot and passengers boarded the helicopter at the ALA for the return flight. The pilot prepared for take-off and lifted off the helicopter more rapidly than he normally did. As the helicopter became airborne, it began to rotate counterclockwise (yaw to the left). The pilot tried to control the yaw but the helicopter quickly turned through 360° and, unable to control it, he made a decision to land the helicopter. The left skid of the descending helicopter subsequently contacted the ground, resulting in a rolling movement that led to the main rotor blades striking the ground… The investigation did not identify any airworthiness issues with the helicopter and it was considered that the loss of control was not attributable to a mechanical issue. It was also determined that the prevailing light winds did not contribute to the loss of control. The pilot reported that he did not lift the helicopter into a balanced hover and tried controlling its yaw mainly with the cyclic control instead of through the full application of opposing right, tail rotor pedal. Management of unanticipated yaw in helicopters with shrouded tail rotors (Fenestron) is the subject of the manufacturer’s guidance and learnings from similar accidents.

The pilot had 315 total flight hours, including 227 hours on the EC130.

Accident involving EC120B at Ballina, New South Wales, on 8 December 2013

The EC120B helicopter rolled onto its side during landing, resulting in substantial damage to the helicopter. The ATSB 

AO-2018-026 (8.38 MB)

report stated:

On 8 December 2013, … [an EC120B] helicopter, registered VH-VMT, departed from a property 16 km north of the Ballina/Byron Gateway Airport, New South Wales for a local flight. On board the helicopter were the pilot and two passengers. At about 1555, the helicopter returned to the property from the north, overflew and approached to land on a heading of about 340º. The pilot reported that the wind was from the north, at about 20 kt. When about 3 ft above ground level, the pilot reported that he entered the hover with an airspeed of less than 10 kt and with full engine power selected. Immediately after, the helicopter began to yaw to the left. The pilot applied right anti-torque pedal to counteract the yaw and reduced the engine power to idle. The helicopter continued to yaw left and the pilot applied full right anti-torque pedal but was unable to arrest the rotation. The helicopter rotated left about 90° before the left skid lowered and contacted the ground. It continued to rotate and rolled onto its right side. The helicopter was substantially damaged and the pilot and passengers were able to evacuate uninjured…

The pilot had 550 total flight hours, including 280 hours on the EC120B. The pilot reported that they had recently been operating a Eurocopter AS350 helicopter, which required less anti-torque pedal input than the EC120B.

Accident involving EC130 at Deer Isle, United States, on 1 August 2009

The EC130 helicopter was substantially damaged during a forced landing. The NTSB report ERA09LA436 stated: 

The helicopter departed a private yacht and was flying along an island shoreline at approximately 400 feet above mean sea level when the pilot entered an out-of-ground effect hover and initiated a left pedal turn. The helicopter started turning faster than commanded, and the pilot was unable to regain control. The helicopter subsequently lost altitude and impacted the water. Prior to impacting the water, the pilot deployed the emergency skid mounted floats to prevent sinking. According to the pilot, "the accident was totally pilot error with no mechanical malfunction." Examination of the wreckage confirmed no evidence of any mechanical malfunction or failure… The National Transportation Safety Board determines the probable cause(s) of this accident to be: The pilot's loss of directional control during an out-of-ground-effect hover. 

The pilot had 680 total flight hours in rotorcraft, and 55 hours on the EC130.

Accident involving EC120B at Skogn Airport, Norway, on 25 May 2018

The EC120B helicopter rolled over during landing, resulting in substantial damage. The Accident Investigation Board Norway (AIBN) published an English summary, which stated: 

The helicopter came out of control in connection with landing. It rotated uncontrolled before it ended up on the side, after the left skid had first hit the ground. There were two people on board. The commander was uninjured while the passenger suffered minor cuts. The helicopter was substantially damaged. Examinations of the helicopter have not revealed technical findings that can explain the loss of control. The Accident Investigation Board Norway finds it probable that the phenomenon of Loss of Tail rotor effectiveness (LTE) may have occurred after the commander failed to correct the helicopter using the right pedal. The AIBN believes that the commander's low experience level contributed to the situation, which was not interrupted in time. 

Additional information from the full report (in Norwegian) included: 

  • The pilot had 143 total flight hours and 8 flight hours on the EC120B (3 hours in command). The pilot’s other experience was on the Robinson R44.
  • The pilot reported applying full right pedal input to oppose the left yaw and then lifted the collective, which required additional power and increased the yaw to the left.

Safety analysis

On 15 May 2025, an Airbus EC120B helicopter was operated at Porepunkah aerodrome, Victoria, for planned private flight to Albury with the pilot and one passenger on board. During take-off into a hover the helicopter entered a left yaw. Attempts by the pilot to correct the yaw with the right pedal were ineffective and the helicopter entered an uncontrolled spin. The right skid struck the ground leading to a dynamic rollover. Both occupants evacuated without serious injury. The following analysis examines how a limited recency on type and skill decay contributed to the loss of control during take-off.

Skill decay

Aircraft type specific handling skills can deteriorate after periods of non-use (Childs and others, 1986; Wang and others, 2013). This effect has been shown in studies conducted during the COVID 19 pandemic which found that pilots underestimated skill decline after a period of extended absence (Mizzi and others, 2024). A similar underestimation is likely to have influenced the pilot’s expectation of yaw response in the EC120B. 

In contrast to procedural skills for simple tasks, more complex tasks such as monitoring, detecting changes and predicting system behaviour typically take longer to acquire and may decay faster (Klostermann and others, 2022). The pilot reported completing a pre‑flight pedal check and was aware significant pedal input was required, however the pilot’s expectations of the aircraft yaw response were likely shaped by the handling characteristics of CTR aircraft, with lower anti-torque pedal demands. 

In response to the yaw, the pilot attempted to gain height and reported increasing the collective. This action led to a corresponding rise in engine power. The increased power output and increased main rotor blade angle amplified the reaction torque and therefore the rotation in yaw to the left. 

With more power to the main rotor, less was available to the tail rotor and therefore the effectiveness of the right pedal input was reduced, allowing the continued helicopter rotation that resulted in ground contact and dynamic rollover.

When the pilot increased the collective on the accident flight, it is almost certain that the range of pedal movement required to arrest the unanticipated yaw outpaced the pilot’s input.

Recency

Although the pilot had extensive helicopter flying experience and was licenced to operate the aircraft, the pilot had not flown an EC120B aircraft type for about 15 years. Having recency on the Robinson R44 helicopter, the yaw control characteristics of the EC120B were sufficiently different to produce effects in excess of the pilot’s expectations. The EC120B yawed to the left, rather than the right, on application of power and required a larger opposite pedal input to arrest the yaw. Being highly experienced in rotary wing operations, this likely increased the pilot’s perception of their ability to operate the helicopter type, even though they had not operated the aircraft type for several years. 

It is likely that the lack of recency on the EC120B led to a degradation in the skill required to counter unanticipated yaw in an aircraft, where the pedal input required was much greater due to the Fenestron design.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving Eurocopter EC120B, VH-JDZ, at Porepunkah aerodrome, Victoria, on 15 May 2025.

Contributing factors

  • The pilot did not anticipate the performance of the design difference of the EC120B. Almost immediately after lifting off, the pilot was unable to counter the helicopter’s left yaw resulting in ground contact and dynamic rollover.
  • Limited recent flying experience on this helicopter type degraded the pilot’s ability to manage the controls effectively. The pilot was unaware that this lack of currency had diminished their competence to safely operate the aircraft type.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • pilot of the accident flight
  • passenger on board at time of accident
  • Civil Aviation Safety Authority
  • aircraft manufacturer
  • maintenance organisation for VH-JDZ
  • Bureau of Meteorology.

References

Airbus (2020). Fenestron versus Conventional Tail Rotor (CTR) for helicopters equipped with a main rotor rotating clockwise when seen from above. (Safety Information Notice 3539-I-00). Airbus S.A.S. Retrieved from Microsoft Word - 3539-I-00-Rev-0-EN.doc

Arthur Jr, W., Bennett, J. W., & Stanush, P. .. (1998). Factors that influence skill decay and retention: A Quantitative Review and Analysis. Human Performance, 11(1) 57-101.

Childs, J., & Spears, W. D. (1986). Flight-skill decay and recurrent training. Perceptual and motor skills, 62(1), 235-242.

Klostermann, M. C., Conein, S., Felkl, T., & Kluge, A. (2022). Factors influencing attenuating skill decay in high-risk industries: a scoping review. Safety, 8(2), 22.

Mizzi, A. L. Lohmann, G., & Carim Junior, G. (2024). The role of self-study in addressing competency decline among airline pilots during the COVID-19 pandemic. Human Factors, 66(3), 807-817.

Wang, X. D. (2013). Factors influencing knowledge and skill decay after training: A meta-analysis. In Individual and team skill decay. Individual and team skill decay , 68-116.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the pilot
  • the passenger
  • Bureau d'Enquêtes et d'Analyses pour la sécurité de l'aviation civile
  • Civil Aviation Safety Authority
  • Airbus. 

Submissions were received from:

  • the pilot
  • the passenger
  • Bureau d'Enquêtes et d'Analyses pour la sécurité de l'aviation civile.

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     The EC120B Colibri was originally manufactured by Eurocopter in 1995. Eurocopter was purchased and became Airbus Helicopters in 2014. Airbus Helicopters ceased production of the EC120B in 2017.

[2]     Yaw: the motion of an aircraft about its vertical or normal axis.

[3]     Dynamic rollover: a helicopter is susceptible to a lateral rolling tendency. It begins when the helicopter starts to pivot laterally around its skid or wheel while in contact with the ground. Once the critical angle, typically around 5–8° is exceeded, the helicopter rolls over, often too quickly for any corrective pilot action.

[4]     Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.

[5]     Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.

[6]     Stators are the ‘blades’ that you can see inside the Fenestron duct that never move and are designed to direct airflow.

[7]     Loss of tail rotor effectiveness (LTE).

Occurrence summary

Investigation number AO-2025-023
Occurrence date 15/05/2025
Location Porepunkah Aerodrome
State Victoria
Report release date 06/11/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Loss of control
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Eurocopter
Model EC120B
Registration VH-JDZ
Serial number 1352
Aircraft operator Dewpoint Investments Pty Ltd
Sector Helicopter
Operation type Part 91 General operating and flight rules
Departure point Porepunkah Aircraft Landing Area, Victoria
Destination Albury Airport, New South Wales
Damage Substantial

Collision with water involving Robinson R44, VH-CTT, 13 km east of Barwon Heads Airport, Victoria, on 2 May 2025

Summary

The ATSB is investigating a collision with water involving Robinson R44, VH-CTT, 13 km east of Barwon Heads Airport, Victoria, on 2 May 2025.

The draft report internal review process has been completed. The draft report has been distributed to directly involved parties (DIPs) to check factual accuracy and ensure natural justice. Any submissions from those parties will be reviewed and, where considered appropriate, the text of the draft report will be amended accordingly.

Following the external review process, the report is approved by management before being sent to the ATSB Commission for final approval. Once approved, the final report is prepared for publication and dissemination and released to DIPs prior to its public release. 

The final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.

Last updated:

Occurrence summary

Investigation number AO-2025-022
Occurrence date 02/05/2025
Occurrence time and timezone 1007 Australian Eastern Standard Time
Location 13 km east of Barwon Heads Airport
State Victoria
Report status Pending
Anticipated completion Q4 2026
Investigation level Short
Investigation type Occurrence Investigation
Investigation phase Final report: External review
Investigation status Active
Mode of transport Aviation
Aviation occurrence category Abnormal engine indications, Collision with terrain, Engine failure or malfunction, Loss of control
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Robinson Helicopter Co
Model R44 II
Registration VH-CTT
Serial number 12599
Aircraft operator Helicopter Adventures Pty Ltd
Sector Helicopter
Operation type Part 133 Air transport operations - rotorcraft
Activity Commercial air transport-Non-scheduled-Joyflights / sightseeing charters
Departure point Barwon Heads/Geelong Aircraft Landing Area, Victoria
Destination Barwon Heads/Geelong Aircraft Landing Area, Victoria
Injuries Crew - 1 (serious), Passengers - 2 (Serious)
Damage Destroyed

Collision with terrain involving Wolf Pitts S1-11X, VH-PVX, Avalon Airport, Victoria, on 28 March 2025

Last updated:

Final report

Report release date: 30/06/2026

Investigation summary

What happened

On 28 March 2025, the Sky Aces formation aerobatics team, which consisted of 4 Pitts‑type aircraft operated by Paul Bennet Airshows, was performing a display at the Avalon Australian International Airshow, at Avalon Airport, Victoria. A Pitts S1-11X, registered VH‑PVX, was one of the 4 aircraft. 

During the aerobatic display, the pilot of VH-PVX entered a triple avalanche manoeuvre, which is a loop with 3 snap rolls at the top. The pilot completed the snap rolls, then attempted to complete the loop. The aircraft collided with the ground resulting in substantial damage to the aircraft and serious injuries to the pilot.

What the ATSB found

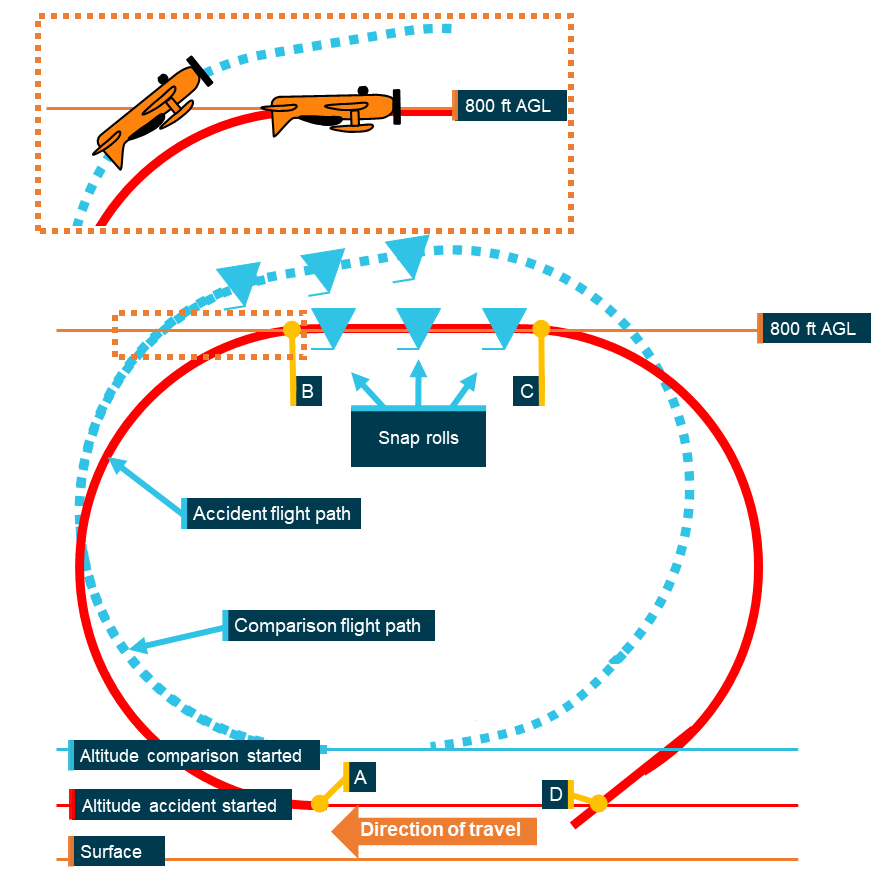
The ATSB found that the aircraft had a lower nose attitude during the snap rolls, which was likely a result of starting the first half of the loop 100 ft lower than the previous commencement height of 200 ft. While the snap rolls were commenced at approximately 800 ft, which was similar to comparison flights, the low nose attitude limited the aircraft’s ability to climb and resulted in the pilot finishing the snap rolls at about 200 ft lower. From the lower height, the pilot then completed the final part of the loop, with insufficient height to safely recover from.

The ATSB also identified several factors that increased the emergency response times to reach the pilot. Although it was unlikely that this additional time affected the consequences of the pilot’s injuries, these factors could, however, affect survivability in a similar circumstance.

What has been done as a result

The event organiser is in the process of redesigning the pyrotechnic area for future airshows to provide clearly identified routes of entry for emergency services to safely access the pyrotechnic field if necessary. This will involve updating transport and emergency management plans, as well as providing briefings to all emergency services agencies and onsite personnel. The organiser will also adopt similar requirements for aerobatic displays to those instituted by the United Kingdom Civil Aviation Authority, with exceptions provided on a case-by-case approval. These include minimum height requirements based on aircraft performance and pilots having ‘gate’ parameters or check altitudes set for all critical junctures of an aerobatic manoeuvre. Further, the organiser is proposing to stage an ambulance with the Aviation Rescue Fire Fighting Services to reduce accident response times.

Safety message

The accident highlights that, although the nature of low-level aerobatics is a high-risk activity, those who participate in these activities can reduce risk by using personal minimum safe heights. This may include:

  • setting and adhering to minimum safe heights for the commencement of manoeuvres
  • confirming the aircraft’s height before commencing a manoeuvre 
  • confirming height prior to reaching a point of no return and having an exit strategy if the height is below the pilot’s minimum
  • undertaking regular reviews of your own and other team members’ in-flight video recordings and engaging in regular debriefing of these, particularly checking that selected minimum commencement height are adequate.

Additionally, any risks identified that may impact the emergency response, should have appropriate controls put in place to ensure responders can act quickly and effectively.


The investigation

The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On the afternoon of 28 March 2025, the Sky Aces formation aerobatics team, which consisted of 4 Pitts‑type aircraft operated by Paul Bennet Airshows, were performing a display at the Avalon Australian International Airshow, at Avalon Airport, Victoria. The 4‑ship1 formation included the Pitts S1‑11X aircraft registered VH‑PVX.

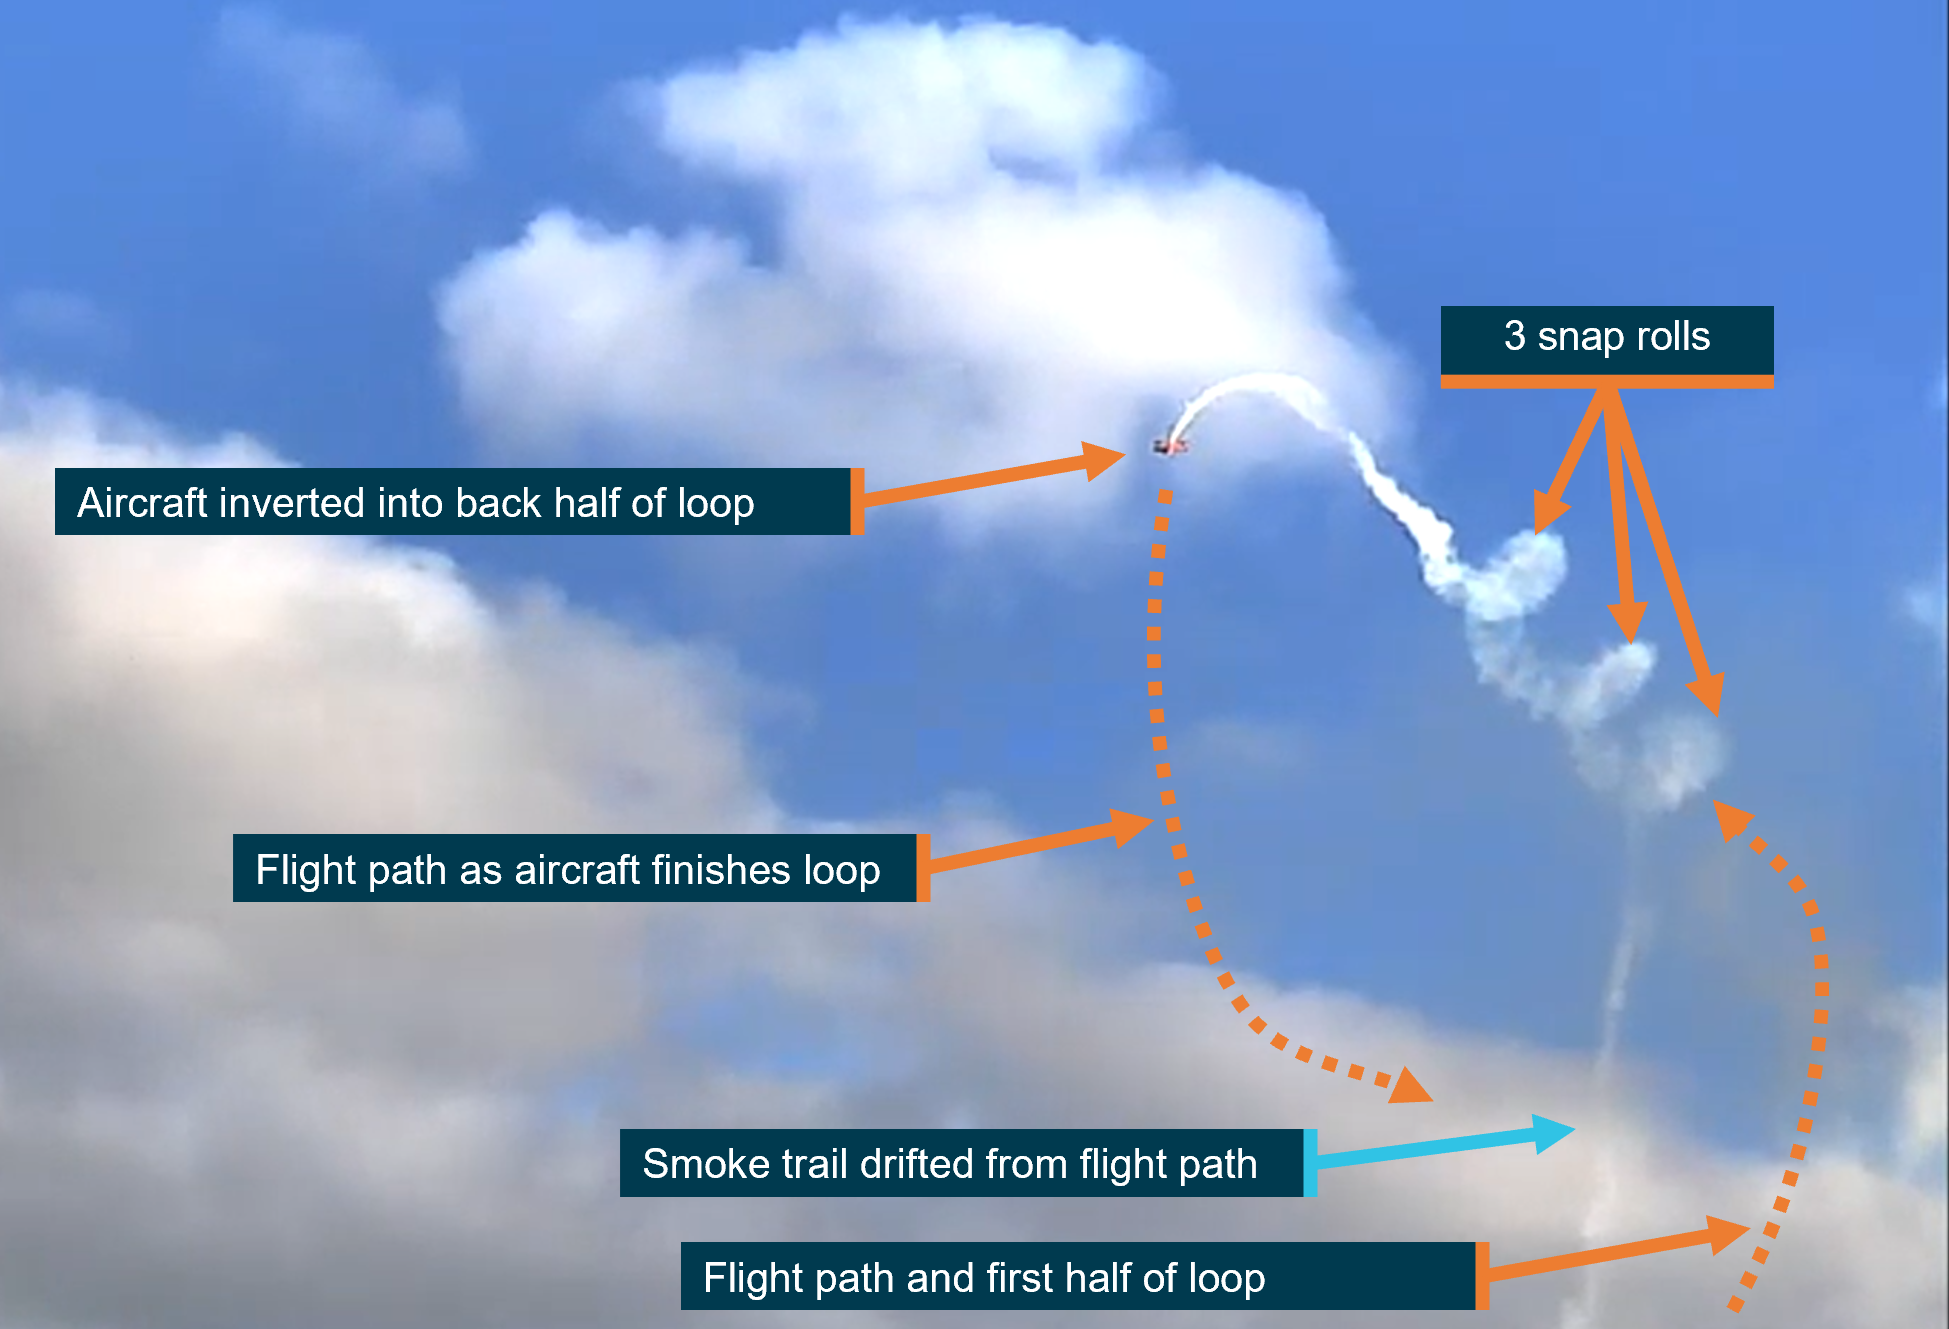
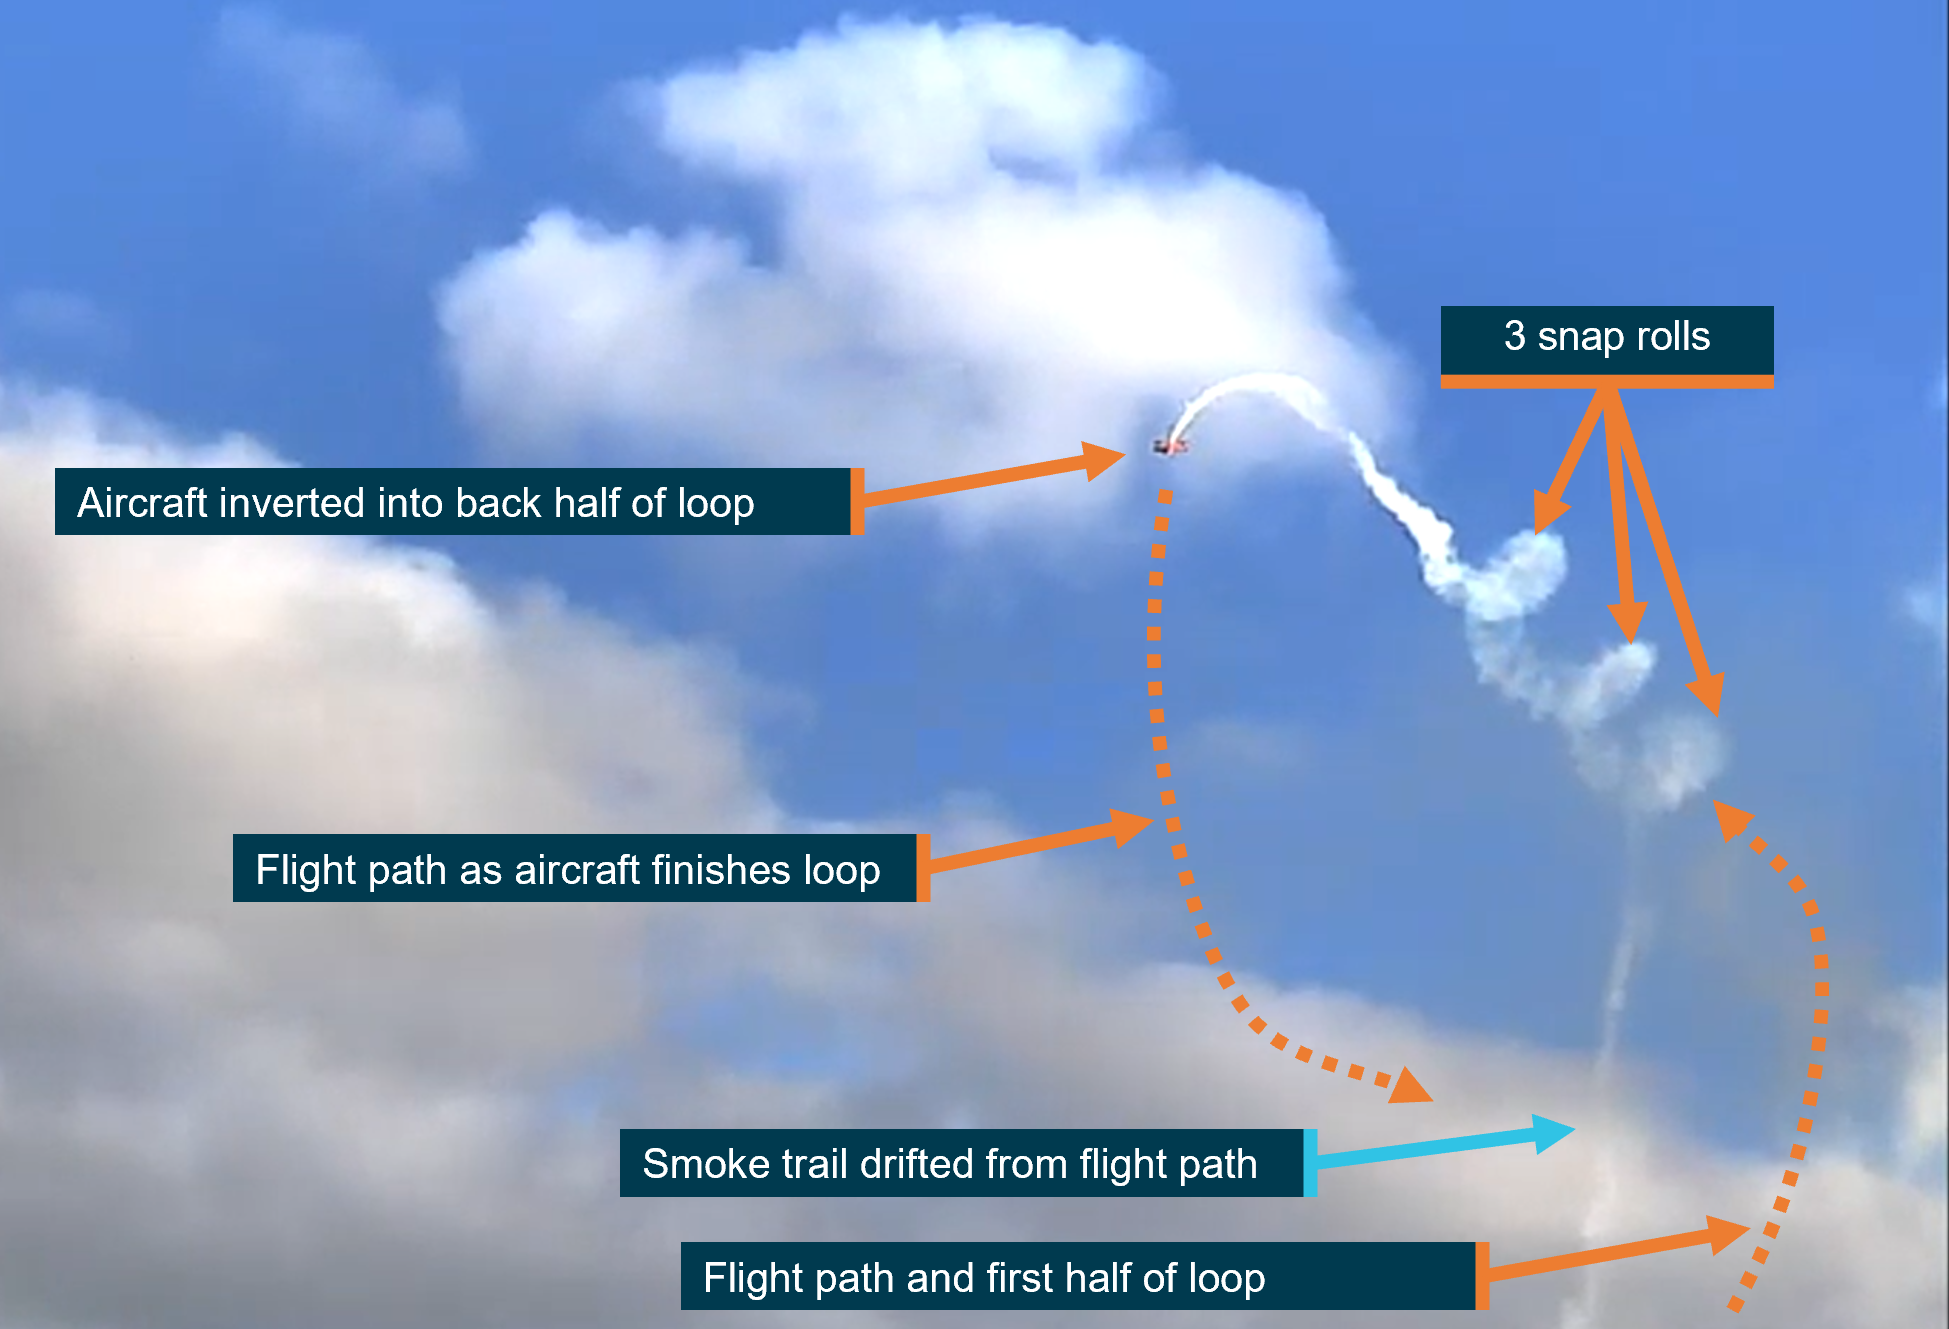
VH-PVX and another aircraft became airborne at about 1710 local time. At about 1715, the pilot of VH‑PVX departed the formation, to start a solo routine. During this solo routine, the pilot planned to complete an aerobatic manoeuvre known as a triple avalanche. The triple avalanche was a combination of a loop with 3 snap rolls2 at the top (Figure 1). The snap rolls were entered and exited from an inverted position.

Figure 1: A successful triple avalanche manoeuvre performed by the pilot in VHPVX on 26 March 2025

Image shows a successful triple avalanche completed by VH-PVX at Avalon Airshow during the flight validation process. It is annotated to show what the manoeuvre should look like.

This is a still image extracted from a video recording of the validation flight (see Validation flight). Source: AMDA, annotated by the ATSB

The pilot entered the first half of the loop from approximately 100 ft above ground level (AGL) (see Recorded information). At the top of the loop, while in an inverted position, the altimeter showed that the aircraft was approximately 800 ft. The pilot then initiated 3 snap rolls, during which the aircraft drifted toward the show line (see Air display information). The pilot finished the snap rolls inverted with the aircraft banked away from the show line. They then began the descending part of the loop, however, they had insufficient height to recover. At about 1717, the aircraft collided with terrain, resulting in substantial damage to the aircraft (Figure 2).

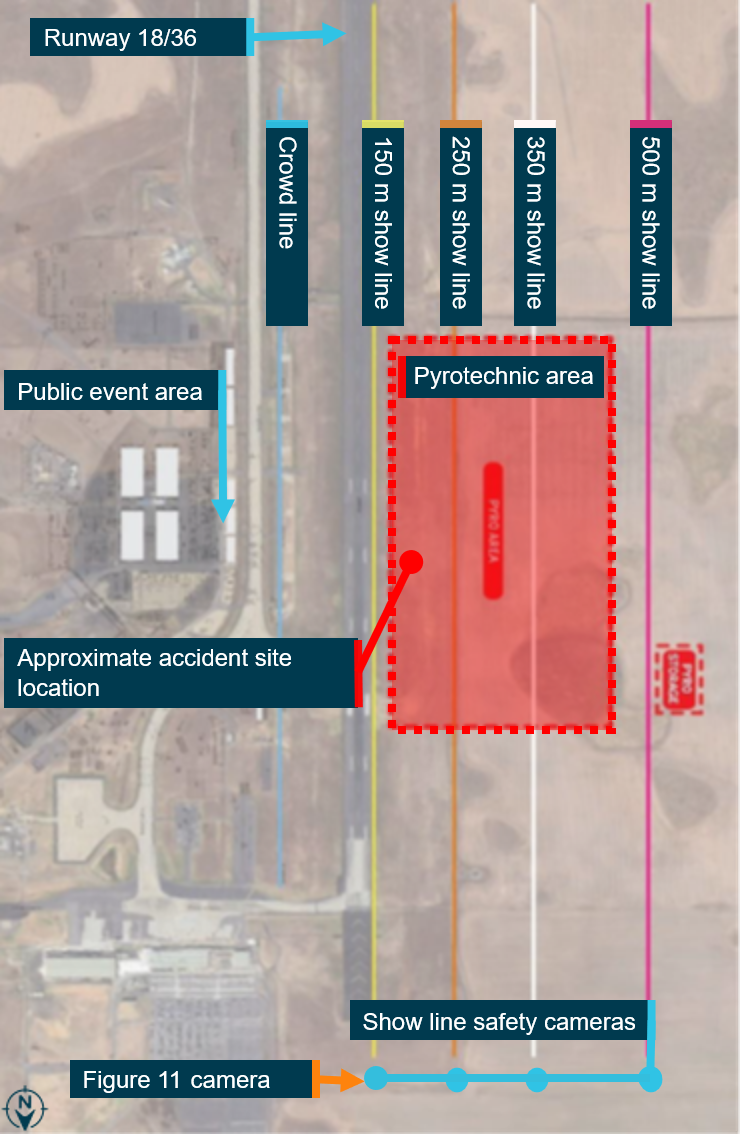
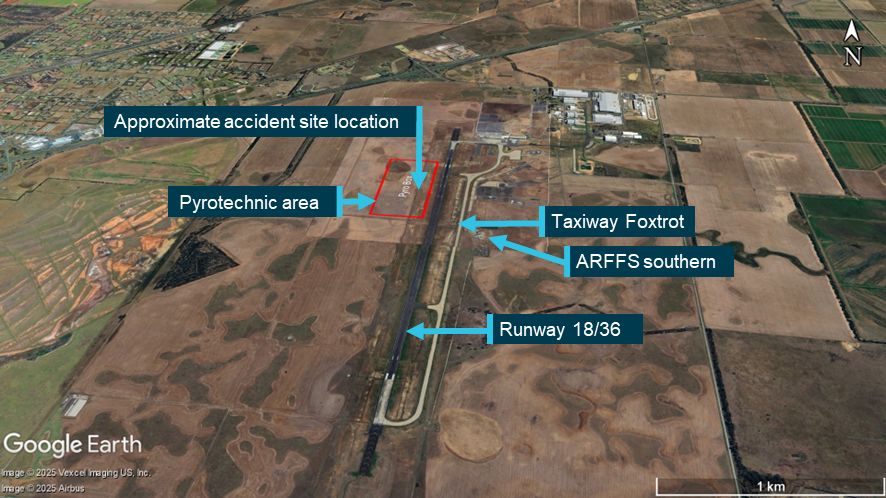
The aircraft came to rest upright, west of runway 18/36, within an area that had been designated for fireworks and other pyrotechnics. The pyrotechnic team members were first to arrive at the accident site. They reported a strong smell of fuel and extricated the pilot from the aircraft. The Aviation Rescue Fire Fighting Service (ARFFS)3 arrived a short time later. The pilot was airlifted to hospital and sustained serious injuries. They reported that they had no recollection of conducting the accident manoeuvre.

Figure 2: Aircraft wreckage

VH-PVX at the accident site, the image shows the extent of the damage resulting from the collision with terrain.

Source: ATSB

Context

Pilot information

The pilot held a Commercial Pilot Licence (Aeroplane) issued in 1999, and a current class 2 aviation medical certificate, which was suitable for the operation type. They completed a single-engine private instrument rating in August 2023, which fulfilled the requirements of a single-engine flight review. The pilot’s logbook showed they had approximately 2,248 hours of total flight experience. 

The pilot had a formation aerobatics flight activity rating issued in 2015 and was approved to conduct aerobatics without an altitude restriction. They held design feature endorsements including tailwheel and manual propeller pitch control, which were required to operate the aircraft. 

The pilot had competed in aerobatic championships and reported that they had flown with the lead pilot since approximately 2002. More recently they had flown as a part‑time member of the Sky Aces aerobatic team.

Operator information

The operator, Paul Bennet Airshows, was a specialist in aerobatic flying and vintage aircraft displays. They were commonly invited to take part in airshows across Australia and internationally. The Sky Aces formation team had performed at multiple airshows prior to performing at Avalon. In preparation for the Avalon airshow, the Sky Ace formation group practised their routine and completed the flight validation required by the event organiser (see Validation flight).

Aircraft information

General 

The Pitts S1-11X aircraft was a single-seat aerobatic, amateur-built biplane, modified from the Pitts S1-11B, and constructed in Germany in 2010 by Wulf (Wolf) Aircraft. It was powered by a Ly-Con AEIO-540-EXP experimental engine and fitted with a 3-bladed, MTV-6 constant-speed propeller of laminated wood construction. The wings were predominantly made of timber with a fabric covering. They were externally braced against each other and the fuselage using a series of flying wires, landing wires, interplane struts, cabane struts4 and incidence wires. The aircraft type did not have wing flaps fitted and all wings had ailerons. The landing gear consisted of left and right forward main gear and a small tailwheel at the rear. The aircraft was a combination of fabric‑covered wood and metal, as well as composite materials, and was designed for unlimited aerobatics up to +/-10 g.5

VH-PVX (Figure 3) was first registered in Australia in 2015 and issued with a special certificate of airworthiness in the experimental category.6 It had been operated by Paul Bennet Airshows since that time. 

Figure 3: VH-PVX at Avalon Airshow prior to the accident

VH-PVX at Avalon Airshow before it was involved in the accident.

Source: Aircountry

Maintenance

The aircraft was maintained as per Civil Aviation Safety Authority Schedule 5 of the Civil Aviation Regulations and required a periodic inspection every 100 hours or 12 months, whichever came first. The most recent periodic inspection was conducted by an authorised maintenance organisation on 28 February 2025. At the time of the accident, the aircraft had accumulated 303 hours total time in service, about 5 hours of which were since the previous periodic inspection. There were no defects listed on the aircraft maintenance release.7

Altimeter accuracy

In February 2025 the aircraft’s altimeter accuracy was checked during a periodic inspection and found to be within allowable limits. Additionally, about 3 minutes before the accident, the onboard camera showed the aircraft’s altimeter reading approximately 1,200 ft, which was consistent with the automatic dependent surveillance‑broadcast8 (ADS‑B) altitude of 1,214 ft above mean sea level recorded for another of the formation aircraft operating at a similar altitude as VH‑PVX. Flight data was not available for VH‑PVX on this flight.9

Canopy

VH-PVX was fitted with a side‑opening canopy. There were no instructions for opening the canopy visible on the outside of the aircraft (Figure 4 top image). This was contrary to the Civil Aviation Safety Authority Civil Aviation Order 101.28 Airworthiness certification requirements – Amateur-built category aeroplanes, section 3.27 Markings and placards that stated markings were required: 

…on both the outside and inside of each exit door, hatch or canopy, indicating the position of the opening handles with locks fully engaged and also providing essential operating instructions for opening.

An example of such instructions on another aircraft is shown in Figure 4 (bottom image). 

Figure 4: Outside of canopy on VH-PVX (top image) compared with a different aircraft showing opening instructions (bottom image)

Outside of canopy on VH-PVX (top image) compared with a different aircraft showing opening instructions (bottom image)

Source: ATSB

The operator reported emergency services and pyrotechnicians were provided with extraction details prior to every airshow.

Meteorological information

The Bureau of Meteorology provided automated weather observations taken at 1-minute intervals at Avalon Airport during the aerobatic display. Between 1710 and 1717, the highest recorded windspeed was 5 kt with gusts up to 6 kt. The temperature was 30°C, visibility was greater than 10 km, and the atmospheric pressure ranged from 1015‍‍–‍1014 hPa for the period. 

Recorded information

Flight data was recovered from an onboard accelerometer unit fitted to the aircraft. The unit recorded elapsed time and acceleration g‑forces, but the data was inconsistent with the flight behaviour. Therefore, it was not used in the analysis. Various sources of video that captured the accident flight were available, so video analysis techniques were employed to generate flight path estimates of the aircraft during the accident manoeuvre.

The in-cockpit camera recording was found to be the most suitable source for the video analysis. It recorded a partial view of the instrument panel, the back of the pilot and view of the outside. Various features visible in the video with known locations were analysed using commercial camera tracking software10 to determine the path of the camera. Specifically, it produced information on the aircraft latitude, longitude and height above ground for each frame, which was used to create an estimated flight path.

The operator also provided the ATSB with 2 videos from the cockpit of VH-PVX that were recorded with the same pilot flying at a previous airshow. These videos were recorded on a GoPro camera in a similar, but not the same, position as the accident flight (over the pilot’s left shoulder). An analysis of these videos and the accident flight is discussed below. 

Aerobatic manoeuvre

Standard process

The pilot described the normal process they would use to complete the triple avalanche manoeuvre, which included the first half of a loop followed by 3 snap rolls and then the final part of the loop (Figure 1). They stated they would normally enter the loop pulling about 4–5 g, then gradually reduce the g toward the top of the loop to start the snap rolls with a slight nose up attitude. Through the process of completing the snap rolls, it was possible for the aircraft to laterally cross the intended show line (see Air display information). In this circumstance, the pilot reported they usually checked the ground position immediately following the completion of the snap rolls and made corrections if they were no longer aligned with the show line. The pilot indicated their personal minimum height for commencing the snap rolls was 1,000 ft AGL. 

Previous flights

In the 2 previous videos provided, the onboard altimeter showed that the pilot began the first half of the loop at 200 ft AGL, began the snap rolls at 800 ft, and finished the snap rolls at 1,200 ft in one instance and at 1,000 ft in the other. In both videos, the pilot completed the final half of the loop and recovered to straight and level flight above 200 ft.

Also, in the first video, the nose attitude of the aircraft appeared to be further above the horizon at the beginning of the snap rolls when compared with the second video. This resulted in more height gained during the snap rolls in the first video. Prior to commencing the snap rolls, the aircraft appeared to be in a nose up attitude. When the pilot commenced the snap rolls the aircraft continued along a similar trajectory in the direction the aircraft’s nose was pointing before the snap rolls were commenced. That is, when the aircraft nose was pointing above the horizon prior to the snap rolls, the aircraft continued in an upward direction while performing the snap rolls. 

Accident flight
Loop entry height

During the accident flight, the onboard altimeter was visible prior to commencing the snap rolls at 800 ft and just prior to the collision with terrain at 100 ft. However, it was not visible during the entry to the loop, or at the completion of the snap rolls.

Therefore, to establish the height the pilot entered the first half of the loop, the ATSB used a combination of the ATSB’s estimated flight path, the aircraft’s altimeter (when in view of the camera) and the height of the aircraft during other low-level passes throughout the display. Table 1 provides this information at various stages of the accident manoeuvre. Figure 5 is a simplified recreation of the path the aircraft flew on the accident flight and the comparison flights. 

Table 1: VH-PVX manoeuvre sequence

Sequence positionFigure 5 referenceAircraft altimeter reading (ft)Estimated height from ATSB flight path recreation (ft) [1]
Entry to first half of the loopANot visible32
Beginning snap rollsB800772
Finishing snap rollsCNot visible786
0.4 seconds prior to collision with terrainD10047
[1] Specific margins of error in this recreation are not known. To check the validity of the flight path, it was compared against the value seen on the altimeter, which was intermittently visible.

There were discrepancies between the estimated height and the onboard altimeter. Such as during the descent, at 0.4 seconds (Figure 5 D) before the collision with terrain, the altimeter showed 100 ft AGL. At that point, the ATSB estimated height was 47 ft. Although, it was possible that the altimeter was lagging the actual height of the aircraft for the short time it was visible due to the descent rate.

However, it was noted that the low-level passes performed during the display and when the altimeter was visible, the aircraft instrument indicated the pilot was flying at approximately 100 ft. Therefore, it was determined that the entry height to the first part of the loop was likely to be about 100 ft. This was 100 ft lower than seen in the comparison flights.

Figure 5: Comparison of the previous and accident flights, showing the nose attitude when reaching 800 ft when starting the first part of the loop at different heights

Comparison of the previous and accident flights, showing the nose attitude when reaching 800 ft when starting the first part of the loop at different heights

The reference points A, B, C, D refer to Table 1. Source: ATSB

Snap roll height gain

As seen in the previous flights, the aircraft gained approximately 200–400 ft during the snap rolls. This allowed the pilot to start the recovery (final part of the loop) from no lower than 1,000 ft. However, the estimated flight path showed that in the accident flight, this was not achieved.

While there was some margin of error due to the available data sources, the ATSB recreation of the flight path from the onboard video estimated that only around 14 ft of height was gained during the snap rolls.

Attitude comparison

The ATSB compared the aircraft’s nose attitude during the snap rolls in the accident flight with the comparison flights. As the exact position, orientation and settings of the cameras varied between the 3 videos, the ATSB was unable to make a quantitative assessment of the difference in attitude between each of the flights. However, a visual comparison of the videos indicated a noticeable difference in attitude between the accident and comparison flights (Figure 6, Figure 7). Additionally, when the pilot reviewed the onboard video recording of the accident flight with the ATSB, they identified that the nose was low on the first snap roll. 

Figure 6 shows the accident flight nose attitude is closer to the horizon when starting the snap rolls than seen in the comparison flight. Figure 7 shows that the accident flight finishes the snap rolls with a lower nose attitude than the comparison flight. Although, it is harder to make a comparison in this image due to the bank angle on the accident flight.

Figure 6: Aircraft’s nose attitude when starting the snap rolls for the accident flight (top image) and a comparison flight (bottom image)

Image at top is of VH-PVX nose attitude during the accident manoeuvre just prior to conducting the snap rolls. Image at bottom is VH-PVX on a different day at the same point in the same manoeuvre except that the nose attitude appears much higher above the horizon.

Source: Operator, annotated by the ATSB

Figure 7: Aircraft's nose attitude when finishing the snap rolls for the accident flight (top image) and a comparison flight (bottom image)

Image at top is of VH-PVX nose attitude during the accident manoeuvre just after conducting the snap rolls. Image at bottom is VH-PVX on a different day at the same point in the same manoeuvre except that the nose attitude appears much higher above the horizon.

Source: Operator, annotated by the ATSB

Final loop segment and recovery

To recover from the triple avalanche, the pilot needed to have sufficient height after the snap rolls to complete the final part of the loop without entering an aerodynamic stall or colliding with terrain. The comparison flights showed this height increase could be achieved during the snap rolls.

Summary of comparison flights 

Table 2 provides a summary of the comparisons made across the 3 videos supplied by the operator.

Table 2: Summary of comparison data

Sequence positionComparison flight 1Comparison flight 2Accident flight
Entry speed to first half of the loop165 kt160 kt>165 kt
Entry height to first half of loop200 ft200 ft100 ft[2]
Nose attitude commencing snap rollsHighest of the 3[2]Similar but lower than comparison 1[2]Lowest of the 3[2]
Beginning snap rolls height800 ft800 ft800 ft
Finishing snap rolls height1,200 ft1,000 ft814 ft[2]
[2] ATSB estimated values   

Wreckage and impact information 

The aircraft collided with terrain on a grassed area west of runway 18/36, in a location of the airport designated as the pyrotechnic box (seeAir display information). In this area, there were multiple pyrotechnics ready to be used in the Sky Aces show, along with many boxes of fuel that were planned to be ignited during the ‘wall of fire’ display later that evening.

A ground scar, approximately 95 m long, was on a south-south-west heading (Figure 8). The aircraft tumbled around the nose and came to rest upright and oriented toward north, almost opposite the direction of the impact sequence and debris trail. The initial impact point occurred about 10 m from the fuel boxes within the pyrotechnics (Figure 8).

Figure 8: Overview of pyrotechnics and point of VH-PVX collision with terrain

Overview of pyrotechnics and point of VH-PVX collision with terrain

Source: Royal Australian Air Force No 1 Security Forces Squadron, annotated by the ATSB

An image taken from the onboard camera showed that the aircraft was in close proximity to the pyrotechnics before (Figure 9) and at the point of the collision with terrain. 

Figure 9: VH-PVX just prior to collision with terrain showing proximity to pyrotechnics

The image shows VH-PVX just prior to the collision with terrain. It shows the aircraft's proximity to the pyrotechnics which were at the accident site.

Source: ATSB

The ATSB conducted a preliminary examination of the aircraft at the accident site, but due to access restrictions for the operational airport and airshow, the wreckage was then relocated to a secure facility for detailed examination. Examination of the wreckage identified:

  • There was no evidence of any defects or failures that may have been present before the impact, and which could have contributed to the development of the accident.
  • The uppermost section of the canopy windshield was fractured partly from the accident sequence and then from first responders accessing the cockpit.
  • The engine mounts had fractured, with the engine remaining tethered by the main fuel line, engine controls and wiring loom. 
  • The propeller hub remained attached to the engine and fragmentation of the propeller blades was indicative of the engine providing power at the time of the collision.
  • The forward main landing gear had permanently splayed outward, the tailwheel strut exhibited some upward deflection, the engine sump cover had fractured, and the lower fuselage section had sustained compression damage, consistent with a hard landing in an upright orientation.
  • The upper wings had separated from the aircraft, with the wing spars fracturing outboard of the cabane strut attachment. The lower wings sustained impact damage but remained secured to the fuselage.
  • The rigid lines between the fuel tanks and selector valve were fractured, resulting in post-accident leakage of fuel. However, the fuel tanks remained intact and there was no post-impact fire.

Air display information

General

Held every 2 years over 6 days, the Avalon Australian International Airshow combined Australia’s largest aviation, aerospace and defence industry trade exposition with a 3-day airshow. The event was organised by the AMDA Foundation (AMDA), which was the chosen name to reflect the consolidation of Aerospace Australia Limited and Industry Defence and Security Australia Limited.

AMDA provided a briefing on airshow operations and safety to all airshow pilots prior to the airshow. This included the expected timetable of display events, pilot responsibilities, display area information, manoeuvre limitations, minimum heights, minimum weather conditions and holding areas. It also included a brief of the emergency procedures and airshow terminology that would be used to terminate displays in the event of an emergency.

Event operations centre

AMDA had created an emergency response plan, which stated:

The priority of the EOC [event operations centre] Manager and Chief Warden in an emergency is to support the emergency control agency and provide clear communication to the Area Wardens within each event zone.

The emergency response plan defined a potential or declared emergency as:

An emergency is when there is a potential incident or incident that could be beyond the ability of the normal day to day management structure. An emergency is described as any incident that:

• Has the potential to cause or is causing loss of life and extensive damage to property, infrastructure or the environment.

• Has the potential to have or is having a significant adverse consequence for the Airshow event, guests, staff and aircrews.

• Requires the involvement of two or more emergency control agencies to respond to a class of emergency as defined in the Emergency Management Act 2013.

     - Class 1 Emergency

     - Class 2 Emergency

It further stated the roles and responsibilities of the event operations centre as follows:

The EOC Manager is required to monitor activity across the precinct and deploy additional resources to assist or deal with incidents as they are reported or identified through CCTV or the AMDA Call Centre.

These include managing critical security, medical or safety incidents which may require a higher level of resources, real time monitoring or a significant management focus. These incidents can occur multiple areas and require deployment of specialised or centrally managed resources.

The EOC Manager is responsible for delegating roles and responsibilities within the EOC to ensure appropriate resources are managing each incident and can escalate to Victoria Police as required.

Designated areas

Designated areas were mapped on Avalon Airport to assist in segregating the airshow from spectators. The airshow had several displays that used pyrotechnics, including the Sky Aces routine. The pyrotechnics detonation area was located to the west of runway 18/36 inside the flight display area. Show lines were created to assist aircraft with conducting displays at an appropriate distance from the crowd (150 m, 250 m, 350 m and 500 m). The show line to which a display could be performed to, was determined by the aircraft’s speed during the display. Cameras were placed on each show line and monitored to ensure aircraft were conducting their displays at a safe distance from the spectators (Figure 10).

Figure 10: Avalon Airport designated areas

Avalon Airport designated areas

Source: AMDA, annotated by the ATSB

The display pilot briefing provided by AMDA stated that aircraft with a maximum display speed between 101 kt and 200 kt could conduct their display as close to the crowd as the 150 m show line. At the time of the accident manoeuvre, the pilot was performing at about 160 kt and performing close to the 150 m show line.

During the snap rolls, the aircraft moved towards the 150 m show line. When the pilot reviewed the accident video, they believed they attempted to correct this, which was also evident from the show line video (Figure 11).

Figure 11: VH-PVX reference to 150 m show line, shows the aircraft moving towards the show line, then away from the line

The image is a recreation of several images which showed the flight path of VH-PVX during the accident manoeuvre. The view is from the 150m show line camera.

The image is made from several images overlaid on each other to show the sequence of VH-PVX. The VH-PVX label shows the first position of the aircraft in the manoeuvre sequence. Source: AMDA, annotated by the ATSB

Validation flight 

AMDA required that participants in the airshow successfully complete a validation flight prior to the public display. On 26 March 2025, the Sky Aces formation team satisfied this requirement, which involved the pilot completing their solo display including the accident manoeuvre in VH-PVX. The validation report had not noted any concerns about the routine or ability of those involved to successfully perform it on the day of the show. There was no comparison video available as evidence of the heights the manoeuvre was performed at during the validation flight.

Event risk assessment

AMDA conducted a risk assessment for the airshow and identified multiple hazards.  Some of the associated risks identified that were relevant to the accident included:

• pyrotechnic display operator injured/killed by aircraft wreckage and/or flare debris impact into pyrotechnic area during airshow

• aircraft/vehicle malfunction or crash during atypical flying display

• vehicle or aircraft transits across the pyro [pyrotechnic] box bursting or igniting flammable liquid explosives

• blocking ARFF [Aviation Rescue Fire Fighting Services] route out of the fire station (Figure 12) with resultant impact on ARFF emergency response times. 

Risk controls were implemented by AMDA to reduce either the likelihood or consequences of the identified hazards, which included:

  • pyrotechnics placed outside the runway strip
  • minimising pyrotechnician personnel in the pyrotechnic area during the airshow
  • a briefing provided to airshow pilots
  • having emergency services in attendance including ARFFS
  • AMDA’s emergency response plan
  • pilots flying in displays were experienced and were required to complete a validation flight.

To ensure taxiway Foxtrot (Figure 12) remained clear for ARFFS units leaving the southern fire station in an emergency, aircraft movements to/from the southern tarmac were controlled by Airservices Australia air traffic control.

Figure 12: Avalon Airport taxiway and ARFFS southern location 

Avalon Airport taxiway and ARFFS southern location

Source: Airservices Australia and Google Earth, annotated by the ATSB

Furthermore, Ambulance Victoria (AV) was contracted to attend the airshow to perform the following roles:

• to manage the pre-hospital impacts of the event through on-site AV resources and transport capability (if required)

• to mitigate the impact of the event on AV’s service delivery to the surrounding community; and

• to ensure that if an incident occurs at the event which evolves into a major emergency, there is an AV presence on-site to manage the pre-hospital response and emergency medical treatment as required, rapidly and effectively.

Survival aspects

Emergency response

An emergency response was activated at 1717 following the accident. Table 3 shows the sequence of events of the emergency response.

At 1718, the pyrotechnicians were first to arrive onsite. The pyrotechnicians were trained in first aid and were able to extricate the pilot from the aircraft, which they determined was necessary due to the strong smell of fuel and their assessment of a possible subsequent fire.

The pyrotechnicians reported having difficulties in opening the aircraft’s canopy, as the opening mechanism was not obvious from the outside. The onboard video showed that the pyrotechnicians took approximately 50 seconds to forcefully remove the canopy, which appeared to have already been damaged in the accident sequence.

At the same time, the ‘crash alarm’ was activated by the air traffic controller and the ARFFS dispatched 2 tenders11 from the southern fire station and one tender from a temporary northern dispatch area. The northern ARFFS response tender crew reported they were unable to use taxiway Bravo while trying to access the accident site as a departing air transport flight was obstructing the taxiway. Instead, the crew opted to use the airport perimeter track and reached the accident site at approximately the same time as the ARFFS tenders responding from the southern side. The ARFFS reported increased response times due to the accident occurring inside the pyrotechnics area and navigating the associated hazards to ensure the safety of the responders. 

When the accident occurred, AV ambulances were already on location at the airshow. However, AV reported that their response time was impacted due to the need to wait for an escort to the scene as the airport remained active to assist with landing of the other formation aircraft. Avalon Airport and AMDA reported the delay was due to the escort waiting for the ambulance to make safe access. The ATSB could not verify the difference in these accounts, but the first ambulance arrived onsite at 1731.

Table 3: Emergency response sequence

TimeResponse action
1717Accident occurred and event operations centre was advised 
1718Crash alarm activated by Airservices air traffic controllers
1718ARFFS dispatched
1718Pyrotechnicians arrived onsite
1719ARFFS stopped short of the pyrotechnic area and assessed the situation
1720Pilot extricated from the cockpit by pyrotechnicians
1721ARFFS arrived at the site
1729Ambulance escorted to accident site
1731First ambulance arrived onsite
1731Ambulance Victoria took control of the emergency response and requested helicopter emergency medical services (HEMS)
1736Second ambulance arrived onsite
1756HEMS dispatched from Essendon Airport (about 50 km away)
1801Ambulances relocated to helicopter extraction point
1822HEMS arrived at Avalon Airport
1906HEMS arrived at the hospital
Pilot injuries

The pilot sustained serious head, chest, abdominal, spinal and leg injuries requiring hospitalisation and long-term rehabilitation. The pilot was wearing a 5-point restraint and a cloth flying cap. 

ATSB analysis based on estimates of aircraft speed, impact angle, attitude, and energy absorption, indicated that the vertical acceleration experienced by the pilot would normally result in serious injuries, in addition to moderate to serious injuries from the horizontal component. 

The tail wheel was the initial impact point followed by the main landing gear, underside of the fuselage, fuel control unit and propeller. During that initial impact, the pilot’s seat crushed 5–8 cm into the fuselage, as the main landing gear spread, distorting the lower fuselage and fracturing the airframe. The pilot’s spinal injuries were almost certainly the result of the vertical impact forces. The gascolator (fuel strainer), located directly beneath the pilot’s seat, pierced the seat base and cushion, but its contribution to the pilot’s injuries could not be determined. 

The pilot’s left leg injury was consistent with crushing of the footwell during the impact sequence. 

After the initial impact, the aircraft tumbled around the nose (Figure 13), destroying the wings and propeller. The pilot was effectively retained in their seat by the 5-point restraint, minimising flail injuries, and the space around the pilot in the cockpit was retained. However, the canopy fractured and was associated with a superficial scalp injury. Had the pilot been wearing a hard-shell helmet, that injury would probably have been avoided, but it would unlikely have reduced the severity of other injuries. 

Figure 13: VH-PVX during the accident sequence

The image was captured during the accident sequence and shows a snap shot in time of VH-PVX.

Source: David Caird, Herald Sun

Safety analysis

Introduction

The pilot of VH-PVX was conducting low level aerobatics at the Avalon International Airshow when it collided with terrain, resulting in serious injuries to the pilot and substantial damage to the aircraft. 

This analysis will examine the accident flight manoeuvre compared with previous flights. Additionally, the ATSB also reviewed elements of the emergency response, which, although not contributing to the accident, could have resulted in increased severity of injuries in a similar occurrence.

Lower manoeuvre height

The accident pilot had previously completed the triple avalanche manoeuvre (the accident manoeuvre) in VH-PVX. Video evidence showed on at least 2 previous occasions the pilot began the manoeuvre at 200 ft above ground level (AGL), started the snap rolls at approximately 800 ft, gained height during the snap rolls and recovered the aircraft. Conversely, the combined analysis of the accident video and flight path estimated by the ATSB showed that the pilot likely began the manoeuvre at approximately 100 ft, started the snap rolls at about 800 ft, but did not gain height throughout the rolls. Although the pilot stated their minimum was 1,000 ft for starting the snap rolls, all 3 flights showed the manoeuvre starting at 800 ft.

A comparison across the 3 flights indicated that, throughout the snap rolls, the nose attitude was comparatively lower or flatter during the accident flight. This was supported by the pilot’s observations when watching the accident flight onboard video. The lower nose attitude was likely a result of starting the first half of the loop 100 ft lower than the previous commencement height of 200 ft. That is, the extra 100 ft available to the pilot in the first half of the loop meant that the aircraft would have been further through the loop by the time they had reached 800 ft and was therefore in a flatter trajectory. As a result, an estimated 14 ft of height was gained during the snap rolls rather than 200–400 ft as achieved for the previous flights with a higher nose attitude.

As the pilot was unable to recall the events of the accident, it was unclear if they were aware of the reduced height when entering the final part of the loop. However, the onboard video and subsequent collision with terrain showed that the pilot elected to continue the manoeuvre although the aircraft did not gain height during the snap rolls. Consequently, there was insufficient height remaining to complete the manoeuvre before colliding with terrain.

Emergency response

Given the location of the flight display area, it was likely that any accident involving a display aircraft operating to the 150 m, 250 m, or 350 m show lines would occur inside the pyrotechnics area. Therefore, due to the increased risk associated with the pyrotechnics, the emergency crew response times were increased as they navigated the dangerous area while operating on an active airport. 

For example, the Aviation Rescue Fire Fighting Service had to assess the hazards associated with the pyrotechnics to ensure the safety of their personnel and one tender had to use an alternative route to the accident site due to a departing aircraft. Likewise, although ambulances were already in attendance at the airshow, it took approximately 14 minutes for them to arrive at the accident site. Ambulance Victoria reported increased response times due to requiring escorts to reach the accident site, however, it was not clear how long ambulances were stationary waiting for an escort.

In addition, the aircraft did not have instructions on how to unlatch the cockpit canopy from the outside, as required for airworthiness certification. However, first responders managed to pull the canopy open in approximately 50 seconds after they arrived onsite. Instructions for opening the canopy may have reduced this time.

Some of these factors could have reduced the time taken to provide assistance to the pilot. However, on this occasion, the pyrotechnicians extracted the pilot from the cockpit, preventing injuries resulting from a possible fire and ARFFS attended to the pilot within 4 minutes of the accident. Therefore, it was unlikely that the severity of the pilot’s injuries were increased due to the location of the accident.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving Wolf Pitts S1-11X, VH-PVX, Avalon Airport, Victoria, on 28 March 2025.

Contributing factors

  • The triple avalanche manoeuvre was likely initiated at a lower height than on previous occasions resulting in a lower nose attitude when commencing the snap rolls at 800 ft, which was also lower than the pilot’s designated height. As result, the aircraft did not gain sufficient height during the snap rolls to recover from the loop before colliding with terrain.

Other findings

  • While not likely contributing to the severity of the pilot’s injuries, several factors increased the time taken to respond to the accident, including:

- the co‑location of the flight display area with the pyrotechnic detonation area

- the Aviation Rescue Fire Fighting Service had to assess and then safely navigate the pyrotechnics area

- Ambulance Victoria had to wait for safe access to the accident site

- the aircraft did not have visible markings on the outside about how to open the canopy.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence. 

Safety action taken by AMDA (the event organiser)

The event organiser reported pyrotechnic area locations that would be fit-for-purpose would still likely result in future possible airshow accidents occurring in the pyrotechnic area. However, it was in the process of redesigning the pyrotechnic area for future airshows to provide clearly identified routes of entry for emergency services to safely access the pyrotechnic field if necessary. This would involve updating transport and emergency management plans, as well as providing briefings to all emergency services agencies and onsite personnel.

The event organiser will adopt similar requirements for aerobatic displays to those instituted by the United Kingdom Civil Aviation Authority with exceptions provided on a case-by-case approval. These include minimum height requirements based on aircraft performance. Additionally, pilots will also be required to have ‘gate’ parameters or check altitudes set for all critical junctures of an aerobatic manoeuvre, such as the apex of a loop and before committing to ‘pulling through the vertical’ to continue the manoeuvre.

Further, AMDA is proposing to stage an ambulance with the ARFFS to reduce response times for any similar future accidents.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilot of the accident aircraft
  • the lead pilot of the formation
  • the airshow event organiser
  • the maintenance organisation for VH-PVX
  • accident witnesses
  • video footage of the accident flight and other photographs and videos taken on the day of the accident 
  • Airservices Australia
  • Avalon Airport
  • Bureau of Meteorology
  • Civil Aviation Safety Authority
  • Ambulance Victoria.

References

Civil Aviation Safety Authority. (2004). Civil Aviation Orders 101.28Airworthiness certification requirements – Amateur-built category aeroplanes.  https://www.legislation.gov.au/F2005B00951/latest/text

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the pilot of the accident aircraft
  • the other pilots within the formation team
  • the airshow event organiser
  • Airservices Australia
  • Ambulance Victoria
  • Avalon Airport
  • Civil Aviation Safety Authority
  • the maintenance organisation. 

Submissions were received from:

  • another pilot in the formation team
  • airshow event organiser
  • Ambulance Victoria
  • Avalon Airport.

The submission were reviewed and, where considered appropriate, the text of the report was amended accordingly. 

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2026

CC BY logo

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

  1. ^    Ship: refers to multiple aircraft flying in formation together. The preceding number refers to the number of aircraft in the formation.
  2. ^    Snap roll: an aerobatic manoeuvre, which results in the aircraft making one revolution about its longitudinal axis with the aircraft aerodynamically stalled. An aerodynamic stall occurs when airflow separates from the wing’s upper surface and becomes turbulent. A stall occurs at high angles of attack, typically 16˚ to 18˚, and results in reduced lift.
  3. ^    ARFFS: Aviation Rescue Fire Fighting Service provides rescue and firefighting services at select airports within Australia.
  4. ^    The cabane struts connect the upper wings connection to the fuselage and form part of the overall bracing scheme.
  5. ^    ‘g’ is an abbreviation for the acceleration due to the earth’s gravity. A positive acceleration equal to 10 times the earth’s gravity is described as +10 g.
  6. ^    Experimental category: the Civil Aviation Safety Authority can issue experimental certificates to allow specific operations of aircraft, which are not by their nature type certificated or have modifications incorporated that are not yet approved.
  7. ^    Maintenance release: an official document, issued by an authorised person as described in Regulations, which is required to be carried on an aircraft as an ongoing record of its time in service and airworthiness status. Subject to conditions, a maintenance release is valid for a set period, nominally 100 hours time in service or 12 months from issue.
  8. ^    Automatic dependent surveillance‑broadcast equipment transmits real-time operational data from an aircraft’s global positioning system and pressure-sensitive altimeter, which enables air traffic service providers to track aircraft. Airservices Australia recorded the transmissions received by its network of ADS-B receivers. That data could also be received by privately-operated equipment used to feed information to flight tracking websites.
  9. ^    It is common practice during formation flying for only one aircraft to broadcast its position.
  10. ^   SynthEyes is a program for 3D camera tracking, also known as match-moving.
  11. ^   Airport tenders are specialised fire engines that carry large amounts of water, foam and other rescue equipment.

Preliminary report

Report release date: 09/07/2025

This preliminary report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

Summary video

The occurrence

On 28 March 2025, at about 1710 local time, the Sky Aces formation aerobatics team, which consisted of 4 Pitts type aircraft operated by Paul Bennet Airshows, became airborne to perform a display at the Australian International Airshow, Avalon Airport, Victoria. The 4 aircraft began their planned routine and flew several aerobatic manoeuvres in 2 and 4 ship[1] configurations. 

At about 1715, the pilot of VH-PVX departed the formation, as planned, and began a solo routine while the formation of the 3 remaining aircraft relocated to the south for their next manoeuvre. At about 1717, while conducting their solo routine, the pilot began a ‘triple avalanche’ manoeuvre[2] and entered the aircraft into a loop (example shown in Figure 1, 2 days prior using a smoke system). At the top of the loop and from an inverted position, the pilot performed 3 snap rolls[3] with one wing aerodynamically stalled.[4] The snap rolls were completed and the aircraft returned to stable flight while still inverted. It then entered the back half of the loop, however, the aircraft’s descent rate was unable to be arrested before it collided with terrain. The pilot was seriously injured.

Figure 1: A successful triple avalanche manoeuvre performed by the pilot in VH‑PVX 2 days prior to the accident 

Exemplar image of the accident manoeuvre (triple avalanche) which was successfully performed 2 days before the accident flight. It shows the aircraft inverted heading into the back half of the loop prior after completing the 3 snap rolls.

Note: This is a still image extracted from a video recording of the validation flight (refer to section titled Flight validation). Source: AMDA Foundation, annotated by the ATSB

Context

Pilot information

The pilot held a valid commercial pilot licence (aeroplane) and class 2 aviation medical certificate. They successfully completed a private instrument rating in August 2023, which satisfied the requirements of a flight review for single-engine aircraft. Additionally, they had the required flight activity and aircraft design feature endorsements to conduct a formation aerobatic display in the Pitts S1-11X aircraft without a minimum altitude limitation. Their formation aerobatics flight activity endorsement was issued in July 2015. 

The pilot’s logbook, which was completed up to 17 March 2025, showed a total flying experience of 2,248.6 hours. It recorded multiple aerobatic preparation flights in VH-PVX and evidence of participation in other airshows. The pilot had also conducted practice flights for the Avalon airshow between 17 March 2025 and the accident flight.

Aircraft information

The aircraft was a single-seat aerobatic Pitts S1-11X amateur-built biplane, modified from the Pitts S1-11B and constructed in Germany in 2010 by Wulf (Wolf) Aircraft. It was powered by a Ly-Con AEIO-540-EXP experimental engine and fitted with a 3-bladed, MTV-6 constant-speed propeller of laminated wood construction. The aircraft was a combination of fabric-covered wood and metal, and composite fibre structure and designed for unlimited aerobatics up to +/-10 G. 

The aircraft was first registered in Australia in 2015 and issued with a special certificate of airworthiness in the experimental category.[5] It had been operated by Paul Bennet Airshows since that time. The aircraft was to be maintained as per Civil Aviation Safety Authority Schedule 5 and required a periodic inspection every 100 hours or 12 months, whichever came first. The most recent periodic inspection was conducted by an authorised maintenance organisation on 28 February 2025. At the time of the accident the aircraft had accumulated 303 hours total time-in-service, about 5 hours since the previous periodic inspection. There were no defects listed on the aircraft maintenance release.[6]

Meteorological information  

The Bureau of Meteorology provided automated weather observations taken at 1-minute intervals at Avalon Airport during the aerobatic display. Between 1710­ and 1717, the highest recorded windspeed was 5 kt with gusts up to 6 kt. The temperature was 30°C, visibility greater than 10 km, and the atmospheric pressure ranged 1015­–1014 hPa for the period. 

Wreckage and impact information 

The aircraft collided with terrain on a grassed area west of runway 18/36,[7] in an area of the airport designated as the pyrotechnics box[8] (Figure 2) where multiple pyrotechnics were live and were planned to be used in the show. Additionally, there were many boxes of fuel positioned in the pyrotechnic box that were planned to be ignited during the ‘wall of fire’ display later that evening. 

Figure 2: Accident site location

A Google Earth image of Avalon airport. The image is annotated by the ATSB to show where the pyrotechnic box is and where the accident site was located.

Source: Google Earth, annotated by the ATSB

A ground scar, approximately 95 m long, was on a south-south-west heading (Figure 3). The aircraft came to rest upright and oriented toward north, almost opposite the direction of the impact sequence and debris trail. The initial impact point occurred several metres from the fuel boxes within the pyrotechnics array. 

While the ATSB conducted a preliminary examination of the accident site, due to access restrictions for the operational airport and airshow, the aircraft wreckage was relocated to a secure facility for detailed examination.

Figure 3: Accident site overview showing the location of the initial impact mark, pyrotechnics array, and the wreckage of VH-PVX

Accident site overview showing the impact mark and pyrotechnics. The image is a top down view of the accident site.

Source: No 1 Security Forces Squadron, annotated by the ATSB

The aircraft sustained substantial damage from the impact with terrain (Figure 4). Examination of the wreckage at a secure facility identified:

  • no evidence of pre-impact defects with the flight control system or fuselage structure to the extent that could be determined
  • the uppermost section of the canopy was fractured and parts of the airframe had departed the main structure
  • the engine had separated from the airframe
  • the propeller blades had fragmented, however, the propeller hub remained attached to the engine
  • the front landing gear was distorted
  • the upper and lower wings had separated, and the lower fuselage section had sustained compression damage
  • the rigid outlet lines from the fuel tanks were fractured resulting in post-accident leakage of fuel.

Figure 4: Aircraft wreckage at the accident site

VH-PVX post accident. The image shows the damage to the aircraft which was a result of the accident.

Source: ATSB

Aerobatic manoeuvre

Practice flights

A review of training videos showed that previous triple avalanche manoeuvres performed by the pilot in VH-PVX were started at approximately 200 ft above ground level (AGL)[9] and an airspeed of 165 kt. The recordings showed the aircraft would reach an altitude of approximately 800 ft prior to entering the snap rolls. The aircraft would climb during the rolls to about 1,100 ft before beginning the back half of the loop. After the accident, the pilot reported that their normal minimum altitude for commencing the snap rolls was 1,000 ft. 

Accident flight

The ATSB recovered a GoPro video camera from within the cockpit of the aircraft that was forward facing and operating during the accident flight. Flight instruments including the altimeter and airspeed gauges were visible in the recording. The recording identified that the pilot set the altimeter to 0 ft (runway reference height) prior to take-off, in accordance with their standard practice when conducting aerobatic manoeuvres.[10] 

During entry to the triple avalanche, the indicated airspeed was approximately 165 kt and the altitude was 100 ft. Just before the aircraft reached its peak altitude, the altimeter was showing 700–800 ft (Figure 5). After this point, the altimeter was blocked from the camera’s view by the pilot’s body position just prior to the collision with terrain.

Figure 5: Still image from the accident flight recording showing the altimeter just prior to the first snap roll during the triple avalanche manoeuvre 

A still image taken from the onboard camera. The image highlights the altitude indicator instrument showing 700–800 ft just prior to the snap rolls.

Source: ATSB

Figure 6 provides a representation of the triple avalanche manoeuvre, showing the loop with the 3 snap rolls (indicated by inverted triangles) and the approximate position where the image shown in Figure 5 was taken. 

Figure 6: Triple avalanche profile and the approximate position in the manoeuvre where the still image from Figure 5 (above) was taken

Triple avalanche profile and the approximate position in the manoeuvre where the still image from Figure 5 (above) was taken.

Source: ATSB

Flight validation

The event organiser required that participants in the airshow successfully complete a flight validation prior to the public display. On 26 March 2025, the formation group satisfied the flight validation requirement, which included the pilot completing the accident manoeuvre in VH-PVX. The event organiser validation report had not noted any concerns about the routine or ability of those involved to successfully perform it on the day of the show.

Emergency response                         

Due to the location of the accident, the pyrotechnicians were nearby and therefore were first to arrive at the aircraft wreckage and assist the pilot. The pyrotechnicians reported that the pilot was wearing a 5-point safety harness, and the cockpit canopy remained closed. They also reported difficulties opening the canopy as there was not an obvious mechanism or external signage on the aircraft to assist them. The first responders reported smelling fuel and observing it leaking from the aircraft, however, there was no post-impact fire.

The Aviation Rescue Fire Fighting (ARFF) service was notified of the accident at 1718 and arrived onsite at 1721. The ARFF provided 3 tenders, 2 responding from the main southern base and one from the northern temporary base. They reported their response times were increased as, while the pyrotechnicians were busy providing first aid to the pilot, they were unable to be safely guided by the technicians through the pyrotechnics area. Additionally, the northern ARFF response vehicle had to deviate around a passenger-carrying jet aircraft on the northern taxiway. ARFF responders took control of the scene and continued providing first aid to the pilot until an ambulance arrived at 1731. The pilot was subsequently transported to hospital by helicopter. 

Further investigation

To date, the ATSB has:

  • examined the accident site and aircraft wreckage
  • interviewed the pilot, operator, and first responders
  • reviewed the meteorological conditions during the display routine
  • reviewed accident and training video recordings.

The investigation is continuing and will include review of:

  • components recovered from the aircraft
  • the aircraft maintenance records
  • video recordings of the accident flight
  • the emergency response plan and actions of the responsible organisations
  • preparation for the display
  • survivability factors.

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken. 

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]      Ship: refers to multiple aircraft flying in formation together. The preceding number refers to the number of aircraft in the formation.

[2]      The triple avalanche aerobatic manoeuvre is a basic loop with 3 snap rolls at the top of the loop. 

[3]      Snap roll: is similar to an accelerated horizontal spin and is essentially an autorotation with one wing stalled.

[4]      Aerodynamic stall: occurs when airflow separates from the wing’s upper surface and becomes turbulent. A stall occurs at high angles of attack, typically 16˚ to 18˚, and results in reduced lift.

[5]      Experimental category: the Civil Aviation Safety Authority can issue experimental certificates to allow specific operations of aircraft, which are not by their nature type certificated or have modifications incorporated that are not yet approved.

[6]      Maintenance release: an official document, issued by an authorised person as described in Regulations, which is required to be carried on an aircraft as an ongoing record of its time in service and airworthiness status. Subject to conditions, a maintenance release is valid for a set period, nominally 100 hours’ time in service or 12 months from issue.

[7]      Runway number: the number represents the magnetic heading of the runway – in this case, 176° and 356°. 

[8]      Pyrotechnics box: an area of the airport designated for pyrotechnics which were used during the airshow to be set-up and detonated.

[9]      Altitude above ground level: as the altimeter setting is set to 0 ft, the altitudes in this report are given above ground level unless otherwise stated.

[10]    Altimeter setting: setting the altimeter to 0 ft on the ground gives the pilot an accurate representation of their altitude above the ground level in that area. 

Occurrence summary

Investigation number AO-2025-017
Occurrence date 28/03/2025
Occurrence time and timezone 1717 Australian Eastern Daylight Time
Location Avalon Airport
State Victoria
Report release date 30/06/2026
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation phase Final report: Dissemination
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Loss of control
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Amateur Built Aircraft
Model Wolf Pitts S1-11X
Registration VH-PVX
Serial number UB001
Aircraft operator Paul Bennet Airshows Pty Ltd
Sector Piston
Operation type Part 91 General operating and flight rules
Activity General aviation / Recreational-Sport and pleasure flying-Aerobatics
Departure point Avalon Airport, Victoria
Destination Avalon Airport, Victoria
Injuries Crew - 1 (serious)
Damage Substantial

Collision with terrain involving Robinson R22 Beta, VH-8BW, 29 km from Southport Aerodrome, Queensland, on 26 February 2025

Final report

Report release date: 04/11/2025

Investigation summary

What happened

On 26 February 2025, a Robinson Helicopter Company R22, with an instructor and a student on board, departed Archerfield Airport, Queensland, to conduct advanced emergency training at Pannikin Island in Moreton Bay, Queensland. 

After practising emergency procedures and low-level flying, the student pilot performed several low-level torque turns, a manoeuvre not originally included in the lesson plan. During the final turn, the helicopter entered a low nose attitude and descended rapidly. The instructor attempted to recover, but due to the low height, was unsuccessful. The helicopter impacted the ground and skidded for some distance before rolling and coming to rest on its left side. The instructor sustained serious injuries and the student sustained minor injuries. The helicopter was destroyed.

What the ATSB found

Low‑level torque turns that were not part of the lesson plan, nor a requirement for commercial licence training, were conducted by a student pilot without a formal pre-flight briefing or guidelines. As the manoeuvre fell outside of the syllabus the ad hoc nature of its inclusion and conduct at the end of the lesson relied on an inflight briefing by the instructor to prepare the student for the exercise. Beginning the low-level torque turn exercise at 50 ft AGL rather than starting higher and working down as the student’s capability improved increased operational risk. Due to the low-level conduct of the exercise, this reduced the available safety margin and placed reliance on the instructor as the only risk control to recover from any unexpected mishandling of the sequence. 

Although the instructor immediately identified that the helicopter was descending rapidly, and took the controls, their actions were unable to recover the helicopter before colliding with terrain. Environmental conditions may have further reduced the safety margin and complicated the low-level recovery.

The operator had no formal process for monitoring the return of training flights. This would likely delay any search and rescue response and reduce post-impact survivability of the helicopter occupants in the event of life-threatening injuries.

What has been done as a result

The operator reported that SARTIME procedures for the flying school have been revised.

Safety message

Ensuring and maintaining sufficient height for recovery is vital in a training environment when a student has limited experience to manage unexpected aircraft or helicopter behaviour. 

All aspects of the lesson should be clearly briefed before flight including planned sequence, risks and hazards to ensure an understanding between instructor and student.

Instructors must rely on conservative in-flight decision‑making to manage risk during flight training operations and to anticipate and be ready to intervene quickly, especially during low-level, or elevated risk manoeuvres.


The investigation

The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 26 February 2025, an instructor and a pilot under instruction (student) were conducting an advanced emergency training exercise in a Robinson Helicopter Company R22 (R22), registered VH-8BW, operated by Utility Helicopters, leased from Heliflite. The training commenced from the operator’s company base at Archerfield Airport, Queensland.

At about 0700, the student conducted a daily inspection of the helicopter under the supervision of the instructor. The intended training flight formed part of the requirements for a commercial helicopter pilot licence and the lesson plan intended to cover advanced emergency procedures. 

At about 0730 the helicopter, with the student flying, departed Archerfield Airport to the south‑east for a designated training area located in Moreton Bay. After reaching the uninhabited Pannikin Island training area, the emergency training commenced with autorotation[1] and tail rotor failure practise. After about 45 minutes, the student then commenced low-level flying practise, completing several clockwise laps around the island. These were completed between 50–100 ft above ground level (AGL) and at a speed of between 60–70 kt. 

Toward the end of the lesson, the instructor recalled that the student requested to practise some agricultural flying operations, which included torque turns.[2] These manoeuvres were not on the lesson plan for the flight, or part of the commercial flight training syllabus, and there had been no plan to conduct them until this point. The instructor demonstrated the manoeuvre before the student took control and successfully completed 4 torque turns. The instructor reported these were conducted at a height of about 50 ft AGL. 

The instructor stated that the low-level turns were conducted across the island roughly in an east–west direction. The exercise was conducted across the prevailing wind direction to avoid a downwind component on each low-level manoeuvre. Torque turns were performed on the eastern side of the island and procedural turns on the western side, with about 4 turns completed at each location. These were executed at a height of about 50 ft AGL. 

As the lesson neared completion, they elected to do one more torque turn before returning to base. The instructor recalled noticing the wind had increased a little and had started gusting but stated that these were not considered abnormal conditions and that both he and the student had flown in these conditions before.

The instructor described that at the top of the last torque turn, they were at a height of 100–150 ft AGL when they began to descend to build airspeed and return to level flight. During the recovery, the instructor noticed that the nose of the helicopter was pointing slightly down toward the ground at a height of about 20 ft. The instructor recalled that they were about to correct the student when a sudden gust of wind increased the rate of descent. Aware of the ground proximity,the instructor immediately took over the controls and recalled moving the cyclic[3] aft to arrest the rate of descent. The instructor reported the helicopter shuddering, shaking, and experiencing a jolt in the collective but was unable to prevent the helicopter impacting the ground. 

Both occupants recalled that everything happened quickly prior to ground contact and that the estimated speed at impact was about 60–70 kt. The instructor recalled that the helicopter impacted hard in a flared nose high attitude and that the stinger[4] contacted the ground first. The helicopter slid along the ground on its skids for about 40–50 m between mangrove bushes before the left skid dug into the muddy ground and dynamically rolled over.[5] The helicopter came to a stop on its left side after numerous rotations and was destroyed (Figure 1). The instructor recalled that the student remained in the helicopter momentarily after impact and then managed to exit and appeared to have had less injuries than themselves so was able to follow instructions to shut down the machine. 

Figure 1: Accident site

A helicopter that has crashed into a mangrove swamp

Source: Student

The student turned off the battery master and assisted the instructor to exit the helicopter. The instructor was unsure if any staff would be in the office and recalled asking the student to use their mobile phone to call for help. They stated that calling the office would not be as effective as calling their partner, as they were aware that several of the staff were away on business. The company was contacted and another helicopter from the base at Archerfield Airport was then dispatched to collect both occupants. About 25 minutes later they were rescued by a colleague who arrived in another helicopter. 

Emergency services were contacted, and an ambulance met the retrieval helicopter on arrival back at Archerfield Airport. Post-accident medical assessment determined that the instructor had sustained serious injuries and the student only minor injuries, both were taken to hospital for treatment.

Context

Aircraft information 

The Robinson R22 is a 2-seat, 2-bladed, single-engine, light utility helicopter manufactured by Robinson Helicopter Company in the United States. It has a maximum all up weight of 622 kg. The R22 is powered by a Lycoming O-360 4-cylinder piston engine that is derated to 131 horsepower for take-off and 124 horsepower for cruise at 2,652 RPM. The R22 is mostly used for private operations, rotary wing flight training and agricultural operations. 

The instructor reported that there were no mechanical issues identified with the helicopter during the daily inspection and pre-flight that would have precluded normal operation.

Flight controls 

The helicopter was fitted with conventional light helicopter flight controls, such as dual cyclic controls for each seat, and a centre‑mounted collective.[6] The engine throttle is connected to collective inputs through a mechanical linkage; when the collective is raised, the throttle is opened and when lowered, the throttle is closed.

Pilot information

Instructor 

The instructor held a commercial pilot licence (CPL-H) helicopter and had been an instructor with the operator for 3 years and 3 months. They began as a grade 3 instructor and progressed to a grade 1 instructor during their employment, logging about 2,800 flying hours. The instructor’s last proficiency check was 29 November 2024. The instructor obtained a low-level rating in 2021 and their low-level flight review for the R22 was valid until 13 November 2025. The instructor held a current Class 1 medical certificate.

Student pilot 

The student pilot had been conducting training with the operator for about 3.5 years. Initially training for a private pilot licence (PPL-H) helicopter, they had not finalised the required ground theory or conducted a flight test. Although they did not hold a PPL-H, they continued training to obtain the required flight hours for a CPL-H. 

Nearing completion of the commercial flight training, the student scheduled their lessons to coincide with their work commitments and they were not regular, but rather when time permitted. Their last lesson before the accident was conducted on 29 January 2025, about 4 weeks prior. They had previously completed advanced emergency training and the intention was to use the lesson as a refresher for CPL-H competency elements. The student reported they wanted to consolidate their low-level flying skills with a goal of working in the agricultural sector. 

At the time of the accident the student had accrued 89 hours of pilot training with the operator. The student reported that about two thirds of all the lessons had been taken with the instructor involved in the accident and the remainder with head of operations (HOO) and one other instructor. 

Meteorological information

Minute-by-minute wind data from the Bureau of Meteorology around the time of the accident indicated generally moderate winds with some directional variability.

Brisbane Airport observations recorded winds at 126°–143° with wind speeds of 9–13 kt, gusting to 18 kt. Similarly, Gold Coast Airport recorded winds at 150°– 208° with wind speeds of 9–14 kt, gusting to 18 kt. The accident site which was located between these two reporting stations (Figure 2) was likely subject to similar wind conditions.

Figure 2: Map showing location of weather stations and Pannikin Island

Map showing location of weather stations and Pannikin Island

Source: Google Earth, annotated by the ATSB

The instructor stated that they checked the weather conditions before departing, and that the wind direction indicated a south‑easterly wind at about 15 kt. On arrival at Pannikin Island, they recalled that the surface wind was observed to be more southerly in direction and felt slightly stronger than 15 kt. 

Downdraught 

Downdraught is a vertical atmospheric condition where a current of air sinks rapidly, leading to sudden changes in conditions at ground level and can produce strong surface winds. Downdraughts can pose a significant threat to rotary aircraft, particularly while manuevering at low level. The most common causes of downdraught experienced by helicopter pilots are due to irregular terrain when combined with strong surface winds, mechanical turbulence,[7] temperature inversions or thermal convection movements. 

Accident site and wreckage

The operator conducted training over Pannikin Island, a designated training area to the south-east of Archerfield Airport. The island is one of several uninhabited islands located in southern Moreton Bay, about 56 km south-east of Brisbane (Figure 3).

The instructor recalled that the Pannikin Island training area extended from sea level to 3,500 ft. The vegetation on the island is mainly mangrove shrubland, with no buildings or power lines in the vicinity, and for this reason was used for low-level training.

Figure 3: Google Earth image of location of Pannikin Island, Queensland

Google Earth image of location of Pannikin Island, Queensland

Source: Google Earth, annotated by the ATSB

The initial ground contact of the helicopter indicated a high‑speed, upright skid contact before further loss of directional control and impact (Figure 4). The student and instructor reported that the speed on touchdown of the helicopter was about 70 kt and was consistent with the skid mark length.

Figure 4: Photograph of impact site

Photograph of impact site

Source: Student

After further impacting mangrove trees, the tail rotor assembly, including tail rotor, gearbox vertical and horizontal stabiliser, separated from the cabin and was reported as being located about 15 m north of the wreckage (Figure 5) and was largely intact. 

Figure 5: Photograph of main and tail rotor wreckage at accident site

Wreckage of empennage and main cabin of helicopter in a mangrove swamp

Source: Student

Post-accident aircraft examination

The operator’s chief engineer carried out an inspection of the helicopter at the accident site before the wreckage was removed. The engineer reported that their examination found no evidence of mechanical issues that could have led to the accident. 

Recorded data

There was no onboard data recording on the helicopter to determine the flight control inputs and their effect on the helicopter during the accident. 

Recorded radar data was available of the helicopter in the training area, however due to the low-level nature of the operation, this was intermittent.

Helicopter exercises and operator’s procedures 

Helicopter pilots are taught a range of manoeuvres as part of their training and licensing requirements. These are typically categorised as either normal, advanced or emergency procedures and are detailed by the Civil Aviation Safety Authority (CASA) for different licence levels and ratings.

In addition to the standard syllabus for advanced emergencies (e.g. autorotation, tail rotor failure), advanced procedures that are not required for the CPL-H may be introduced by flight instructors to extend a student’s capability and confidence. The approved Civil Aviation Safety Regulation (CASR) Part 141 operator exposition did not include torque turns as a requirement to obtain a CPL-H.

Pre-flight briefing

Briefings prior to a flying lesson are an essential part of flight preparation and represent an opportunity to gather, mentally prepare and organise the structure of the upcoming training flight. It is also an opportunity to assess the potential risks and hazards that might arise during normal and emergency operations. Discussion on the procedures to be used in the case of unexpected events disrupting the planned flight operations are also covered, and this prepares and sets student expectations for the lesson.

While pre-flight briefings were normally conducted before each lesson covering the intended lesson sequences, on this occasion the instructor considered a detailed briefing was unnecessary due to the student’s previous experience. Before departure, the instructor and student recalled a brief discussion focused primarily on the weather, but this did not include a formal briefing covering the planned exercises and potential risks. 

The intent of the lesson was to consolidate the student’s prior training and both pilots recalled that the session was to refresh and consolidate advanced emergency procedures. 

Low-level operations 

A low-level operation is defined by regulation 61.010 of CASR as flight at a height lower than 500 ft AGL, other than when taking off or landing, and is not permitted unless the circumstances outlined in sub regulation 91.267(3) of CASR apply to the flight and the pilot is authorised under Part 61 to conduct the operation. Low‑level operations can introduce increased risk for all pilots as the proximity to terrain and reduced margin for recovery intensify the consequences of any deviation from the expected performance. There is also an increased susceptibility to adverse environmental conditions for students with less experience.

Torque turns 

A torque turn is an advanced manoeuvre to quickly complete a 180° change in direction of flight (Figure 6). The manoeuvre begins with a pitch upwards to reduce forward airspeed followed by an application of power to increase altitude. As airspeed decreases, aerodynamic stability is reduced and the increased torque induces yaw.[8] This yaw is used to initiate the turn which continues until the helicopter is facing the opposite direction. Once the turn is complete, the pilot regains airspeed, eases out of the dive and resumes level flight in the new direction. 

Figure 6: Helicopter torque turn flight sequence

Diagram of helicopter showing torque turn procedure.

Source: ATSB

The student reported that their request to conduct the torque turn training was driven by their desire to seek employment in the agricultural domain (aerial application and dispensing operations) after obtaining their commercial licence. They recalled completing several turns successfully before the accident turn. 

However, in response to the draft report, CASA stated that torque turns are not common and are actually avoided in rotorcraft aerial application and dispensing operations, in favour of accurately flown and coordinated procedure turns (see below).

No official height for conducting torque turns in training is provided by CASA, however general guidance provided for starting more advanced or complex manoeuvres is to begin at higher altitudes and reduce once competence is gained.

Procedure turns

A procedure turn is a standard course reversal manoeuvre used to change the helicopter’s direction. ICAO defines the manoeuvre as a turn made away from a designated track followed by a turn in the opposite direction to permit the aircraft to intercept and proceed along the reciprocal of the designated track. Procedure turns may be designated as being made either in level flight or while descending, according to the circumstances of each individual approach procedure. To commence the turn the aircraft would turn off track, maintain airspeed, conduct the turn and turn onto the reverse of the original course. They are sometimes referred to as ‘P turns’ as the flight track looks like a ‘P’ from above.

The Part 61 Manual of Standards competency standards for unit AA2 – Helicopter aerial application operation, specifically requires procedure turns in element AA2.6 – Manipulate helicopter at low level:

(a) manoeuvres helicopter at all speeds below 500 ft AGL, up to and not beyond the limits of the flight-manoeuvring envelope, without exceeding the operating limitations of the helicopter; 

(b) conducts coordinated, smooth procedure (P) turns with varying power settings.

Operator low-level training

In line with the CASA requirements, the operator’s exposition stated that procedure turns were required for advanced low-level training and detailed amongst other manoeuvres that the height range for the conduct of these was between 200 ft and 5 ft AGL. However, no specific minimum height was declared for procedure turns.

There was no reference for torque turns in the operator’s exposition.

Search and rescue

Search and rescue time (SARTIME) is the time nominated by a pilot for the initiation of search and rescue action. Any person deemed to be a responsible person can hold SARTIME for a pilot’s safe arrival. 

There was no regulatory requirement for the operator’s local training flights under CASR Part 91 for a SARTIME, however the absence of a formal flight following process during flight training may have implications for the operator’s duty of care during the operation.

The operator’s head of operations (HOO) reported that a range of tracking systems were used across the operator’s fleet, including satellite trackers and transponders. These devices allowed staff to monitor the location of helicopters during flight and, if a helicopter did not return within an expected time, its position could be quickly determined. A television screen located in the operator’s office displayed tracking data, however, no personnel were specifically assigned to monitor return times or to observe the radar feed.

Many of the flight training lessons were conducted from the operator’s base at Archerfield Airport, where staff could maintain direct visual oversight of helicopter movements. However, as the accident flight was early in the morning, there was only one other instructor conducting flight training and the office staff were not yet on duty.

Some helicopters in the fleet were fitted with electronic locator transmitters and others with personal locator beacons. Under CASR regulations these are mandated for flights greater than 50 NM from the departure aerodrome. The accident helicopter was fitted with a manually‑activated personal locator beacon, however the instructor reported that they were dazed immediately after the accident and did not prioritise the activation.

Safety analysis

Introduction

An instructor and a student were conducting advanced emergency training in a Robinson Helicopter Company R22 (R22) helicopter, registered VH-8BW, at Pannikin Island in Moreton Bay, Queensland. Near completion of the commercial helicopter pilot lesson, the instructor and student agreed to conduct torque turns, an advanced helicopter handling manoeuvre that was outside of the training syllabus. After conducting several torque turns, the helicopter entered an increased low nose attitude during recovery at low altitude which resulted in a collision with terrain and dynamic rollover. 

This analysis will consider decision‑making of the instructor and student and the instructor’s recovery as factors in the accident. 

Decision-making

Instructing is a complex task and flight instructors must balance the benefit to the student’s learning and experience with safe margins of operation in a dynamic and sometimes rapidly changing environment. 

The decision to conduct torque turns was only discussed between the instructor and the student during the flight.

Instructors consider several factors such as student performance, recent progress and training objectives when making in‑flight decisions to alter or vary the training flight plan. While instructors can adapt lessons to suit the student’s progress, deviations from planned activities should be underpinned by clear safety considerations, briefings and effective risk management. 

Effective instructional decision-making balances educational value with operational risk. The instructor assessed the student to be capable of performing the manoeuvres based on their recent progress and performance during the lesson and having completed many previous training hours together. However, this assessment was done during the training flight, limiting the time available for the instructor to fully consider the benefits and risks (including height to conduct the training – see below).   

The benefits of conducting a pre-flight brief of the lesson, especially where training operations are conducted in emergencies is well-established. Such a briefing reaffirms standard operating procedures, promotes predictable behaviour, and sets expectations (Sumwalt and others, 2010). 

The torque turns were not part of the syllabus and were not necessary for the lesson. However, if the decision to conduct them had been agreed before flight, this would have allowed for a full ground briefing to establish the torque turn procedures, discuss the conduct of the manoeuvre and ensure a common understanding of how the practise turns would be conducted. 

Manoeuvre height

Torque turns were outside of the advanced emergency lesson for the operator’s commercial pilot training syllabus and consequently no procedure was identified in the training materials for conducting them during training. The absence of a defined procedure places the reliance on the instructor to become the risk control. In this case there was an increase in risk as the manoeuvre was conducted at a height that reduced the available safety margin and limited the opportunity for recovery when the helicopter entered an undesired state. By contrast, if the manoeuvre had been initiated at a higher altitude, the increased height would have provided more time for the student and instructor to identify, intervene and recover from the undesired aircraft state. Increased altitude when practising a high-risk manoeuvre with a student would allow time for corrective control inputs from the instructor to avoid collision with terrain. 

Beginning the low-level torque turn exercise at 50 ft AGL, rather than starting higher and working down as the student’s capability improved, increased operational risk.

Instructor recovery

During the torque turn, the helicopter exited the manoeuvre in a lower than expected nose attitude. Instructor intervention is a critical control in flight training and is often the final opportunity to regain control of the helicopter. Although the instructor took over control as soon as they recognised the rapid descent rate, the low height on exiting the torque turn limited the time available to arrest the descent before ground contact occurred. Environmental conditions may have further reduced the safety margin and complicated the low-level recovery.

Due to the high speed of the helicopter and approaching vegetation, the instructor likely attempted to slow the helicopter using rear cyclic (as would be normal practice when airborne), however, after skid contact with the ground in an upright attitude, this likely resulted in the main rotor disk flexing and making contact with the tail boom. This resulted in the severing of the tail boom by the main rotor blades, loss of torque control and the front left skid digging into soft soil, leading to a dynamic rollover. 

SARTIME 

The operator had no formal process for monitoring the return of training flights. While many operations were conducted within line-of-sight or in close proximity to the operator’s base, this informal system provided limited assurance that an overdue returning training flight outside of the airport vicinity would be identified. In this case, had the crew been more seriously injured or rendered unconcious, the lack of formal SARTIME and flight following would likely have delayed the initiation of search and rescue efforts and substantially reduced survivability. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving Robinson R22 Beta, VH-8BW, 29 km north of Southport Aerodrome, Queensland, on 26 February 2025.

Contributing factors

  • While conducting commercial training consolidation for low‑level and emergency procedures, the instructor and student agreed to conduct torque turns, which were outside the lesson plan and training syllabus.
  • Without a procedure, the instructor conducted the exercise at an inappropriate low height, which increased risk and did not allow for a margin of error.
  • During the torque turn exercise the helicopter exited the turn in a lower than expected attitude. The instructor assumed control but was unable to prevent a collision with terrain.

Other findings

  • The operator had no formal process for monitoring the return of training flights. This would delay search and rescue response and reduces post-impact survivability of aircraft occupants in the event of life-threatening injuries.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence. 

Safety action addressing SARTIME

The operator has implemented a SARTIME procedure using an application for shared messaging between instructors and staff. For each flight, the instructor records the helicopter registration, flight details and estimated time of arrival back at base. Any delays are communicated through the group and landings are confirmed upon arrival at base or the intended destination. The procedure is documented on the pre-flight board.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • instructor of the accident flight
  • student pilot
  • operator CEO and HOO
  • Civil Aviation Safety Authority
  • Bureau of Meteorology.

References

Sumwalt, R. L. Lemos, K. A., & McKendrick, R. (2019). The accident investigator’s perspective. In Crew resource management (pp. 489-513). Academic Press.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • instructor of the accident flight
  • student pilot
  • operator CEO and HOO
  • Civil Aviation Safety Authority.

Submissions were received from:

  • instructor of the accident flight
  • operator CEO and HOO
  • Civil Aviation Safety Authority.

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Autorotation is a condition of descending flight where the main rotor of a helicopter is driven only by aerodynamic forces with no power from the engine due to engine failure or deliberate disengagement.

[2]     A torque turn is an advanced manoeuvre involving rapid yaw using engine torque to change direction.

[3]     Cyclic: a helicopter control used to tilt the rotor disc allowing the aircraft to move in a particular direction. 

[4]     A stinger, otherwise known as the tail skid, is a protrusion at the rear of a helicopter that is intended to protect the tail boom when landing.

[5]     Dynamic rollover: a helicopter is susceptible to a lateral rolling tendency. It begins when the helicopter starts to pivot laterally around its skid or wheel while in contact with the ground. Once the critical angle, typically around 5–8° is exceeded, the helicopter rolls over, often too quickly for any corrective pilot action.

[6]     Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity. 

[7]     Mechanical turbulence occurs when wind flows over obstacles like mountains or buildings, disrupting smooth airflow and creating bumpy flight experiences. 

[8]     The motion of an aircraft about its vertical or normal axis.

Occurrence summary

Investigation number AO-2025-011
Occurrence date 26/02/2025
Location 29 km from Southport Aerodrome
State Queensland
Report release date 04/11/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Flight control systems, Loss of control, Weather - Other
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22 Beta
Registration VH-8BW
Serial number 4200
Sector Helicopter
Operation type Part 141 Recreational, private and commercial pilot flight training
Departure point Archerfield Airport, Queensland
Destination Archerfield Airport, Queensland
Damage Destroyed

Loss of control and equipment contact with water involving Bell 412EP, VH-VJF, 57 km north-east of Strahan Airport, Tasmania, on 10 March 2025

Summary

The ATSB is investigating a loss of control event involving a Bell 412EP, registered VH-VJF, 57 km north-east of Strahan Aerodrome, Tasmania, on 10 March 2025.

The helicopter was being operated by Coulson Aviation for firefighting operations using a sling-loaded water bucket. While hovering to load the bucket from a river, the helicopter unexpectedly sank about 50 ft. In an attempt to recover, the pilot initiated forward flight but was unable to jettison the load before the longline became taut, causing a sudden stop and an abrupt tail-down motion. This resulted in the external hook and longline making contact with the lower fuselage.

The pilot flew back to the base at Zeehan where inspection identified damage to the helicopter’s fuselage, control tubes for both the engines and the tail rotor. Damage was also identified to the bucket and longline.  

To date, the ATSB investigation has included:

  • interviewing involved parties 
  • retrieving recorded data
  • the collection of other relevant information
  • reviewed recorded aircraft information
  • reviewed the forecast and observed weather conditions
  • reviewed maintenance documentation for VH-VJF 
  • analysed recorded helicopter information 
  • reviewed pilot training delivered by Coulson Aviation.
  • review of Coulson Aviation’s risk controls for bucketing operations in the Bell 412
  • review of Coulson Aviation’s operational and reporting procedures
  • review of Tasmanian Fire Service operational and reporting procedures.

An interim report, which details factual information established during the course of the investigation, was released on 17 March 2026 (see below).

The draft report internal review process has been completed. The draft report has been distributed to directly involved parties (DIPs) to check factual accuracy and ensure natural justice. Any submissions from those parties will be reviewed and, where considered appropriate, the draft report will be amended accordingly.

Following the external review process, any submissions and amendments to the draft report are internally reviewed. Once approved, the final report is prepared for publication and dissemination and released to DIPs prior to its public release.

The final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.

Last updated:

Interim report

Report release date: 17/03/2026

This interim report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Interim reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this interim report is released in accordance with section 25 of the Transport Safety Investigation Act 2003

The occurrence

Prior to the occurrence flight

On 10 March 2025, a Bell 421EP, registered VH-VJF and operated by Coulson Aviation as HT204, was tasked with ground crew support operations on the Canning Peak fire, a sub‑fire of the West Coast fire complex in Tasmania. 

At about 0830, the Tasmanian Fire Service briefed pilots on the weather and taskings for the day while at Strahan Airport. The Air Attack Supervisor (AAS) reported that the 2 Bell 412 helicopters were tasked with the insertion of crews into the fireground (HT201) and then firebombing[1] in support of those crews with a 150-ft longline and bucket[2] (HT204).

At about 0900, both helicopters departed Strahan Airport for Tullah, which was the designated staging area[3] for the activities. Approximately 25 minutes later both helicopters arrived at Tullah. The pilot of HT204 reported shutting down the helicopter and waiting until they were required for firebombing operations. The pilot of HT201 reported picking up a crew and completing an insertion into the fireground before returning to Tullah and remaining on standby in case an extraction was required. 

First fuel cycle

At about 1215, HT204 was tasked with firebombing operations in direct support of ground crew who were undertaking hot and cold trailing.[4] 

At 1226 local time the pilot departed Tullah for hotspots located west of the Murchison River on the south‑east end of the fire. The pilot was the only person on board. The pilot reported that the weather conditions on departure were calm, with a temperature of 22°C and light, variable winds. 

When reaching the dip site[5] the pilot completed one fuel cycle, approximately 10 bucket loads, under relatively stable conditions. The pilot described the dip site as a narrow section of river, approximately 50–60 m wide, with tall trees lining the bank (see also Dip site). The drop zone was located approximately 1 km west of the dip site. 

The pilot then returned to Tullah to pick up an air crew officer (ACO) at 1400 and continued onto the designated air base in Zeehan, which had a sports oval being used as a refuel base (Figure 1).

Figure 1: First fuel cycle and return to Tullah

A google Earth image outlining the flight path from Tullah to the dip site and back. Then the flight path from Tullah to Zeehan.

White line: flight path of the first fuel cycle and return to Tullah. Purple line: flight path from Tullah to Zeehan. Source: Google Earth, annotated by the ATSB

Zeehan air base

During the approach to Zeehan, the pilot noted a significant weather change, with winds shifting to a westerly direction at approximately 30 knots. 

While on the ground, the helicopter was refuelled for the next cycle. At about 1440 the pilot departed Zeehan and returned to the Canning Peak fireground. 

Second fuel cycle and occurrence

The pilot recalled that various dip sites along the river looked similar. Flight data (Figure 2) indicated the pilot initially conducted a descent into an incorrect dip site. The pilot recognised this and undertook reconnaissance to find the intended dip site. Once reaching the dip site, the pilot resumed bucketing operations. 

Figure 2: Second fuel cycle flight path

Second fuel cycle flight path including the incorrect dip point, the reconnaissance flight and the location of the main dip point.

Source: Google Earth, annotated by the ATSB

The pilot reported that, at about 1525, while filling the third bucket load of water, the helicopter had been in a stable hover at about 150 ft above the water, when it unexpectedly sank. The pilot recalled the helicopter sinking approximately 50 ft. To recover control, the pilot applied forward cyclic and upward collective inputs to transition to forward flight and stabilise the helicopter, while aiming to avoid an over-torque event. 

Prior to this manoeuvre, the pilot reported they were unable to jettison the longline, which they attributed to pressing on the button’s ring guard instead of its centre, and the longline subsequently became taut. The helicopter then came to an abrupt stop and the pilot heard a ‘loud clunking noise’. The pilot then recovered the helicopter to a stable hover approximately 30 ft above the water and initiated rearward flight to release the water and retrieve the bucket from the river. The pilot observed an engine torque split[6] and once the bucket and longline were recovered they initiated a climb to clear the surrounding trees. 

The pilot reported that once they had cleared the trees, the torque split levelled back out. They conducted a range of tests to assess controllability and engine performance, including minor adjustments to engine torque. The pilot noted that the tail rotor control pedals felt stiff, however they continued to provide adequate input for sufficient helicopter control. 

The pilot contacted the AAS on the fire common traffic advisory frequency (FCTAF) stating they had a bucket issue and a flight control issue.  

The air attack pilot (who flew the helicopter with the AAS on board) oriented the helicopter to view HT204. The AAS recalled HT204 gaining altitude and tracking away from the Murchison River, over the fire, heading on a bearing south‑west uphill and back to Zeehan. They noted the helicopter was climbing slowly and appeared to be flying irregularly during this period. They reported they had not seen the occurrence as the dip site HT204 was using was beneath and behind the air attack helicopter. 

The AAS contacted the pilot on the FCTAF. The pilot of HT204 reported issues with the helicopter pedals and when asked what their intention was, the pilot reported they were heading back to Zeehan. The AAS acknowledged this and reported they would follow HT204 back. 

The pilot of HT204 assessed available landing options but elected to continue toward Zeehan rather than commit to an off-field landing. This decision was influenced by a previous experience where a potential landing site, assessed from approximately 500 ft, had appeared suitable but proved unsuitable upon reaching around 30 ft. The pilot considered that committing to a landing carried the risk of being unable to complete it safely.

The AAS and air attack pilot discussed possible landing options nearby. However, given the impaired controllability of HT204 and the smaller prepared landing areas on the fireground, they agreed the best action would be to return to Zeehan. 

Return flight

The pilot of HT204 reported that, during the return flight to Zeehan, airspeed was maintained between 65 and 70 kt[7] due to the tail rotor pedals feeling stiff. This would reduce strain on the tail rotor by operating the helicopter at a lower power setting.

The pilot reported continuing the flight toward Zeehan with a plan that, should the situation deteriorate further, the flight would be changed to Strahan Airport as an alternative. Throughout the remainder of the flight, pedal inputs were minimised in an effort to avoid exacerbating the condition.

The AAS described the helicopter’s flight en route to Zeehan as appearing abnormal. In addition to the notably reduced speed, HT204 appeared to be yawing from side to side and maintained an unusually low height above ground. They reported that due to the pilot sounding stressed they did not contact the pilot further.

The AAS recalled contacting the air base manager at Strahan and the air operations manager and advised them of an unknown mechanical malfunction with HT204. They reported that the pilot was still in control, and that they were following HT204 back to Zeehan.

Landing at Zeehan

At about 1548, the pilot conducted a shallow approach to set up a vertical descent to the oval in Zeehan with the bucket and longline attached. During the landing sequence, the ACO secured the bucket and longline and moved it away and forward of the landing zone. The pilot then released the line and allowed the helicopter to sink, utilising available power, which resulted in what they stated ‘appeared to be a satisfactory landing with minimal pedal input required’.

After landing, during the shutdown procedure, the pilot was unable to roll the engine throttles back to idle. While disconnecting the longline from the hook, the ACO observed significant damage to the helicopter’s fuselage structure aft of the external hook. 

The pilot of HT201 recalled that they landed and shut down their helicopter in Zeehan. They observed HT204 still running and the pilot underneath the helicopter assessing damage. They discussed the issue of not being able to roll the engines back and the pilot of HT201 suggested pulling the helicopter’s T-handles.[8] The T-handles were pulled to shut down the engines. 


Context

Pilot information

The pilot held a Commercial Pilot (Helicopter) Licence, with a single engine class rating for helicopters. They held type ratings for the Bell 212, 412 and 427. The pilot’s total aeronautical experience was over 3,000 hours of which 120.6 hours were on the Bell 412. In the previous 90 days the pilot had flown 50.3 hours, all on the Bell 412. 

The pilot was qualified to conduct helicopter firefighting operations and had low‑level and sling operation ratings.

The pilot last completed an aerial application proficiency check on 11 November 2024, which was valid for 12 months, and a low-level helicopter flight review on 4 December 2023. 

The pilot held a valid Class 1 aviation medical certificate, valid to July 2025. The certificate specified that the pilot was to wear distance vision correction while flying, which was being worn on this occasion.

Helicopter information

General information

The Bell Helicopter Company 412EP is a medium‑lift[9] utility helicopter commonly used for firefighting, search and rescue and transport operations. The helicopter had a 4-blade main rotor and 2‑blade tail rotor and was powered by 2 Pratt & Whitney PT6T-3DF turboshaft engines. The helicopter was manufactured in Canada in 2004 and first registered in Australia in 2020. The helicopter was owned by NSW Rural Fire Service (RFS) and operated by Coulson Aviation Australia. 

VH-VJF had accumulated about 4,819 flight hours total time in service and had a current certificate of airworthiness and registration. The helicopter’s technical log indicated no outstanding defects at the time of the accident. 

The helicopter’s multi-role configuration enabled it to be utilised in a range of aerial firefighting tasks, including reconnaissance, winching operations and firebombing using either a belly tank or external bucket system (Figure 3).

Figure 3: NSW RFS Bell 412 EP VH-VJF

Image of the Bell 412 HT204 indicating the location of the FLIR camera, winch, external load system and vertical reference door.

Source: Lesley de Robllard, annotated by the ATSB

On the day of the accident, the helicopter was configured for firebombing operations and was fitted with an external load system, a vertical reference door, and a 150‑ft longline attached to a Bambi bucket[10] (see Bucket and longline information). In addition to these items, the helicopter also had a forward looking infrared (FLIR) camera mounted on the left‑hand side of the helicopter above the skids.

External load system

VH-VJF was equipped with an Onboard Systems International cargo hook suspension system. The system attached to an existing Bell hard point and hung at approximately the centre of gravity. It extended through an opening in the lower fuselage, which was fitted with a protective rubber ring around the edge (Figure 4). This protective ring was used to reduce the risk of damage if the hook hit the edge of the opening.

Figure 4: Onboard Systems International cargo hook suspension system on the Bell 412

Diagram of the Onboard Systems International cargo hook suspension system on the Bell 412.

Source: Onboard Systems International, annotated by the ATSB

The release of the hook could be initiated electrically or mechanically. Normal release was completed by pilot actuation of a push button on the side of the cyclic (Figure 5, left). The button is guarded by a small ring to prevent inadvertent pilot activation. When this button is pressed the latch of the cargo hook is opened. 

In addition to the electrical release, in an emergency a mechanical release can be completed by pushing a small pedal located between the 2 tail rotor pedals at the pilot’s feet (Figure 5, right). This activated a manual release cable attached to the cargo hook.

The cargo hook suspension system was required to be inspected annually or after 100 hours of external load operations, whichever came first. The system was last inspected on 20 February 2025. 

Figure 5: Electrical and mechanical external load release systems

Images of the electrical and mechanical external load release systems.

Left: the electrical release found on the cyclic grip. Right: mechanical release between the 2 pedals. Source: Coulson Aviation, annotated by the ATSB

Coulson Aviation required pilots to test the electrical and manual release system prior to conducting flights for the day. The pilot recalled testing both the electrical and mechanical release the morning of the accident. They stated that both systems were in working order. In addition to the tests, the pilot recalled that when landing at Zeehan after the accident, the electrical release was used to drop the longline and bucket without issue. 

Coulson Aviation reported that both the electrical and mechanical releases of the hook were tested following the accident. Both were reported as serviceable. 

Vertical reference door

The Bell 412EP helicopters are usually flown from the right-hand seat. This configuration is used when pilots are conducting either winching or reconnaissance operations. The helicopters can be modified to include a vertical reference door, which is designed to provide the pilot with a side bubble window and instruments for longline operations from the left-hand seat.

VH-VJF was modified with a vertical reference door in accordance with the Transwest vertical reference door supplement type certificate. This included a bubble window, viewing slot, and instruments and warning lights installed in the door (Figure 6).

Figure 6: Instruments and warning lights installed in the vertical reference door

Image of the instruments and warning lights installed in the vertical reference door, including the dual torque indicator and the triple tachometer.

Source: Coulson Aviation, annotated by the ATSB

In addition to the instruments and warning lights, the type certificate required the installation of several systems to be placed on the left side of the helicopter. This included: 

  • a force trim switch, cargo release switch and automatic flight control system (AFCS) release switch mounted on the left cyclic
  • the torque meter and tachometer from the left-hand instrument panel moved to the vertical reference door
  • an additional mechanical cargo release pedal between the left side pedals.

During the occurrence flight and other firebombing operations, the pilot was operating the helicopter from the left-hand seat, utilising the left cyclic and referencing the flight instruments through the vertical reference door. While conducting the water collection, the torque indicator was visible through the bubble window and could be monitored during the lift. 

Bucket and longline information

The bucket and longline were attached to the external load system via a bow shackle (Figure 7, left). 

The bucket was a Bambi Max bucket with a nominal capacity of 240 US gallons (910 L). The empty weight of the bucket was 137 lb (62 kg) and the maximum gross weight was 2,140 lbs (970 kg).

The collapsable bucket was equipped with multiple selectable drop valves. Pilots were able to use the bucket to split water loads into multiple drops (Figure 7, right) and had the capability to shed the load rapidly.

Figure 7: Longline attachment and Bambi Max bucket

Image of the longline attachment and Bambi Max bucket

Source: Coulson Aviation, annotated by the ATSB

The longline was constructed from high-strength synthetic fibre rope selected for its high tensile strength, low stretch characteristics, light weight, and resistance to heat and abrasion. The line incorporated an electrical cable along the line to control bucket release. The 150-ft length provided vertical separation between the helicopter and the load to reduce rotor downwash disturbance during water pick‑up. 

Forward looking infrared (FLIR) camera

FLIR cameras are used on aerial firefighting aircraft to provide thermal imaging of fire grounds, enabling crews to detect heat sources through smoke, darkness, or challenging terrain. This capability allows operators to identify fire hotspots, monitor fire spread, and support decision-making for resource deployment and suppression strategies.

On the Bell 412s, the FLIR camera was mounted on the left side, just above the skids. Coulson Aviation stated that although the cameras could be removed, they would generally be kept on the helicopters throughout all operations, allowing the ability for the crews to be re-tasked for reconnaissance missions. Some pilots indicated to the ATSB that the camera could partially obscure visibility during bucketing.

Helicopter damage

The ATSB did not examine the helicopter or equipment. Coulson Aviation conducted an examination of the helicopter the morning after the occurrence. The following damage was identified:

  • The #1 engine control tube had sheared at the lower tube end bell crank, resulting in a complete loss of pilot input to the engine.
  • The #2 engine control tube bell crank attachment bracket had detached from the helicopter structure’s securing rib, restricting pilot control of the engine.
  • The tail rotor control rod on the right-hand side of the external hook’s bell crank airframe attachment had broken away, with the primary structure also separated.
  • The main transmission oil cooler pressure line exhibited significant contact damage, however, no splits or leaks were identified.
  • The fuel tank interconnect braided hoses sustained minor contact damage.
  • Multiple aft fuselage drain lines were damaged.

Images of the helicopter indicated that the structural fuselage honeycomb aluminium skin, adjacent to and aft of the external hook, was deformed and had separated from the primary structure (Figure 8).

Figure 8: Helicopter aluminium skin damage

Damage to the helicopter aluminium skin.

Source: Coulson Aviation, annotated by the ATSB

Images revealed indications consistent with contact between the longline and the rear cross tubes of the helicopter. In addition, inspection of the cargo hook and associated bumper stop components identified visible signs of impact damage (Figure 9).

Figure 9: External load system damage

Image of the damage to the external load system.

Source: Coulson Aviation, annotated by the ATSB

In addition, the ring in the middle of the Bambi bucket spoke assembly was fractured in 4 places (Figure 10).

Figure 10: Bambi Max damage to spoke assembly

Image of the damage to the Bambi bucket

Source: Coulson Aviation, annotated by the ATSB

Multiple instances of cable bruising and stretching were reported to have been observed on the bucket cable wiring and attachment eye ends. The ATSB was unable to substantiate the presence of cable bruising and stretching based on the images provided of the cables.   

Weather data

On departure from Strahan Airport, the meteorological aerodrome report (METAR)[11] reported wind west‑north-west at 6 kt, visibility greater than 10 km and no cloud cover. 

The Tasmania Fire Service (TFS) incident action plan indicated that weather on the Canning Peak fire would change from north-westerly to west-south‑westerly by mid‑morning with winds reaching 10 kt by the afternoon (Table 1).

 Table 1: Canning Peak fire forecast

Local timeTemperature (°C)Dew point (°C)Wind directionWind speed (kt)Wind gust (kt)
08001412N58
09001713NNW810
10001914NW814
11002214WNW814
12002314W1016
13002514W1016
14002613WSW1016
15002613WSW814
16002613WSW810

The AAS reported that on the day of the accident the wind was calm, there was no turbulence and ‘great’ visibility. A change in wind direction was noted from mid-morning changing from northerly to south-westerly, however this was expected based on the forecast. They recalled the area in which the aircraft were working in was protected from south‑westerly winds due to the topography. They reported no feedback from pilots regarding the weather or any other environmental conditions on the day. 

The pilot of HT201 reported there were blue skies and fairly light winds on the day of the accident. They recalled that although they were not bucketing on this day, during previous bucketing operations in the same valley, the wind conditions were variable and the wind would shift ‘back and forth’. 

 A weather station atop Mt Inglis, approximately 15 km north of the operating area (Figure 11), recorded south‑south-westerly winds at 5.7 kt gusting to 11.4 kt at the time of the accident. 

Figure 11: Canning Peak weather station location to dip site

Image of the location of the weather station in relation to the dip site and the staging area.

Source: Google Earth, annotated by the ATSB

Fireground information

The West Coast fire complex originated from 24 individual ignitions sparked by dry lightning strikes on 3 February 2025, across Tasmania’s remote western and north‑western regions. These separate fires were grouped into a single complex for coordinated management due to their proximity, shared weather influences, and overlapping spread patterns. 

There were 4 primary firegrounds that accounted for the majority of the burnt area: the Canning Peak fireground, the Yellowband Plain fireground, the Mount Donaldson fireground, and the Corinna Road fireground. Each represented a distinct sector with unique terrain, vegetation types, and behavioural characteristics. These firegrounds collectively contributed to the complex’s total footprint of nearly 95,000 hectares.

Canning Peak fireground

The Canning Peak fireground was located in a more elevated and vegetated zone close to the Cradle Mountain area and in proximity to sections of the Overland Track. This sector featured rugged alpine-influenced terrain that complicated direct ground access, leading to heavy reliance on aerial suppression tactics. 

Figure 12: Canning Peak fireground

Outline of the Canning Peak fireground.

Black outline indicates area which has been burnt by fire. Source: Tasmania Parks and Wildlife Service, annotated by the ATSB

Day of accident

On the day of the accident HT201 was the designated winching helicopter and HT204 was part of the bucketing helicopters on the fireground. There were 6 helicopters (3 x AS350, 1 x Bell 412 (HT204), 1 x Bell 212, 1 x BK 117) bucketing within a 2 km proximity of each other intermittently. In addition, the air attack helicopter was on scene overhead.

The helicopters were distributed across 4 separate circuits, with 5 separate dip points, seperate individual and shared targets and some shared ground crew. 

Dip site

The pilot reported that the general location for a dip site was provided prior to commencing operations on the fireground, with selection of the specific section of river within that area being at their discretion. The pilot advised that they chose this dip site location on the river as it was relatively wider than other areas and they had used this section as a dip site on the days preceding the accident.

HT204’s dip site was approximately 700 m from the next nearest dip site with working helicopters. The dip site was approximately 1 km south‑east of the drop zone, along the Murchison River. Google Earth images indicate the river width at the dip point was approximately 20 m (Figure 13).

Figure 13: Dip site location on Murchison River

Google Earth image of the dip site and drop zone.

Source: Google Earth, annotated by the ATSB

The pilot described the dip site as a narrow section of river, approximately 50–60 m wide, with tall trees lining the bank. They reported that there were limited locations deep enough to operate the bucket, which constrained where they could dip and they stated they had used the same dip point on the days prior.

In addition, the river contained very little water at the time, allowing clear visibility to the riverbed. They stated that they could not recall whether any tree branches or rocks were present in the riverbed during the operation. Despite the presence of tall trees, the pilot indicated that the area was accessible to the aircraft and considered it one of the better dip sites along the river. They also noted that the turnaround time from the dip point to the fireground was approximately one minute. 

The AAS described the dip site as a section of river with trees approximately 30–60 m tall on either side. They recalled that the pilot was the only one using the dip point and the only helicopter in the circuit. In previous weeks, when different crews had flown the same helicopter on similar missions, no pilots had reported any problems with the dip point. Based on the dips that were observed, the occurrence pilot appeared to be performing them safely and adequately.

Recorded data

Multiple independent data sources, including TracPlus satellite-based tracking logs, FlightAware ADS-B derived positions, and OzRunways electronic flight bag recordings, were cross‑referenced and correlated to reconstruct the helicopter’s flights throughout the day and to approximate the entry and exit angles into and out of the bucketing site.

TracPlus

The helicopter was fitted with a TracPlus surveillance system, which provided real-time tracking through a satellite or mobile phone network. It reported position, altitude, and speed at set time periods, in this case every 15 seconds. 

OzRunways

The OzRunways application recorded the helicopter’s position at regular intervals of approximately 5 seconds throughout the day, capturing parameters including latitude, longitude, groundspeed, track, and truncated altitude (in 100 ft increments) where connectivity permitted. However, no position data was recorded during the bucketing operations (Figure 14). This absence of recorded data was likely attributable to the helicopter operating at very low levels, down to around 150 ft above ground level, while conducting repeated drops in mountainous terrain.

Figure 14: OzRunways flight data

Google Earth image indicating the flight path data recorded by OzRunways.

Source: Google Earth, annotated by the ATSB

FlightAware

The FlightAware flight tracking data captured the helicopter’s en route flight to the bucketing site, as well as the subsequent low-level manoeuvres involving repeated water dips and drops. Position reports were recorded at irregular intervals ranging between approximately 8 seconds and 40 seconds[12] during these operations.

In addition to the TracPlus data, FlightAware was incorporated into the data analysis. The differing sampling rates and coverage characteristics of the 2 systems together produced a more complete reconstruction of the helicopter’s flight circuit during the second fuel cycle (Figure 15).

Figure 15: Second fuel cycle data from TracPlus and FlightAware

Google Earth image indicating the flight path data recorded by TracPlus overlaid with data from FlightAware.

Pink line: TracPlus data. Blue line: FlightAware data. Source: Google Earth, annotated by the ATSB

Further investigation

To date, the ATSB has conducted the following activities:

  • interviewed the pilot and other Coulson Aviation personnel
  • interviewed the air attack supervisor from Tasmania Parks and Wildlife Service
  • reviewed recorded aircraft information
  • reviewed the forecast and observed weather conditions
  • reviewed maintenance documentation for VH-VJF
  • analysed recorded helicopter information
  • reviewed pilot training delivered by Coulson Aviation.

The investigation is continuing and includes:

  • review of Coulson Aviation’s risk controls for bucketing operations in the Bell 412
  • review of Coulson Aviation’s operational and reporting procedures
  • review of Tasmanian Fire Service operational and reporting procedures.

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2026

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Firebombing: The National Aerial Firefighting Centre states that firebombing is the dropping of fire suppressant or fire retardant from an aircraft to assist with the control or suppression of a fire. 

[2]     Firebombing with a bucket, often known as ‘bucketing’, requires filling the bucket by lowering it into a water source, and emptying it as required at the flame front. 

[3]     A staging area is a designated location where aircraft and crews temporarily assemble and wait for tasking to active fires.

[4]     Hot and cold trailing is a task requiring identification of hotspots along the fire perimeter, opening these areas/smouldering ground fire up with hand tools and directing pilots to drop buckets atop the burning material to prevent further fire spread.

[5]     A dip site is a designated water source where helicopters equipped with buckets can collect water for aerial firefighting. These sites can be natural bodies of water, such as lakes, rivers, or ponds, or artificial sources like reservoirs and water tanks. Their key requirements are sufficient water depth, accessibility, and proximity to the fire to maximise efficiency.

[6]     Engine torque split in a multi-engine helicopter is where there is an unequal proportion of total main rotor torque shared between each engine through the gearbox.

[7]     The Bell 412EP cruise speed is 122 kt.

[8]     The T-handles are a red handle which pilots pull in an emergency to shut off fuel, hydraulics, and other systems to an engine while arming the fire extinguishing bottles. 

[9]     A medium-lift helicopter is one capable of carrying moderate loads, typically between 2,000 kg and 5,000 kg. 

[10]    A Bambi bucket is a collapsible water bucket suspended beneath a helicopter, used to collect and drop water during aerial firefighting operations. 

[11]    METAR (Meteorological Aerodrome Report) is a routine aerodrome weather report issued at half‑hourly intervals. The report ordinarily covers an area of 8 km radius from the aerodrome reference point.

[12]    This update rate arises from the way FlightAware processes ADS-B data: although equipped aircraft transmit position messages nominally every second, the displayed track depends on signals received by a network of ground stations. In remote hilly terrain, at low altitudes down to around 150 ft AGL, terrain shadowing, ridges, valleys, and line-of-sight limitations can prevent some transmissions from being captured reliably. As a result, FlightAware relies on the most consistent available reports, leading to longer effective intervals of 25–40 seconds or more during intermittent low-level reception.

Occurrence summary

Investigation number AO-2025-013
Occurrence date 10/03/2025
Occurrence time and timezone 15:25 Australian Eastern Daylight Time
Location 57 km north-east of Strahan Airport
State Tasmania
Report release date 17/03/2026
Report status Interim
Anticipated completion Q4 2026
Investigation level Systemic
Investigation type Occurrence Investigation
Investigation phase Final report: Approval
Investigation status Active
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Control issues, Loss of control, Miscellaneous - Other
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Bell Helicopter Co
Model 412EP
Registration VH-VJF
Serial number 36329
Aircraft operator Coulson Aviation (Australia) Pty Ltd
Sector Helicopter
Operation type Part 138 Aerial work operations
Activity General aviation / Recreational-Aerial work-Firefighting
Departure point Tullah Helicopter Landing Site, Tasmania
Destination Zeehan Aircraft Landing Area, Tasmania
Injuries None
Damage Substantial

Loss of control during marine pilot transfer operations involving Agusta A109E, VH-XUM and bulk carrier Star Coral, about 200 km north-east of Mackay, Queensland, on 25 February 2025

Final report

Report release date: 29/07/2025

Investigation summary

What happened

On the morning of 25 February 2025, an Agusta A109E helicopter was conducting a marine pilot transfer operation on the inbound bulk carrier Star Coral at Blossom Bank pilot boarding ground, about 200 km north‑east of Mackay, Queensland.

At 0901 local time, during take‑off from the ship with 2 pilots on board, the helicopter developed severe vibrations. The pilots discontinued the take-off but their attempts to recover control of the helicopter were unsuccessful. The helicopter came to rest in an upright position on the helideck, having spun more than 90° counterclockwise from its initial heading, and sustaining substantial damage. The pilots and ship’s crew were unharmed.

What the ATSB found

The investigation did not identify any airworthiness issues with the helicopter and it was considered that the loss of control was not attributable to a mechanical issue. 

The ATSB found that the vibration was likely the result of the helicopter entering ground resonance, a phenomenon that dissipates when airborne, while it was in the process of departing from the ship. The discontinuation of the take‑off, after the onset of the vibration, probably resulted in the loss of control and subsequent damage to the helicopter.

What has been done as a result

The operator has added new guidelines on ground resonance to its procedures. The guidelines include procedures for recognising and recovering from ground resonance and feature case studies and video resources for training purposes. 

The operator has also developed an updated procedure for training and checking flight briefings that will include confirming the roles of each pilot, procedures for transferring aircraft control between pilots, and actions to be followed in the event of an actual emergency.

Safety message

The occurrence highlights the dangers of ground resonance, a potentially catastrophic phenomenon that can occur in helicopters with fully articulated rotor systems. Typically, the onset of ground resonance is sudden and if the pilot does not take immediate corrective action, a loss of control can rapidly occur. 

The occurrence also highlights the importance of proper coordination between a helicopter’s pilots when responding to abnormal or emergency situations. This is particularly pertinent for situations where the pilot flying is not the pilot in command. Ideally, the pilots’ individual roles and responsibilities for emergency response and flying duties should be well established prior to the flight. 


The investigation

The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

At about 0730 local time on 25 February 2025, the 229 m bulk carrier Star Coral arrived at the Blossom Bank pilot boarding ground, about 200 km north‑east of Mackay, Queensland (Figure 1). The ship waited to embark a coastal marine pilot by helicopter for its inbound transit of the Great Barrier Reef via Hydrographers Passage.[1] It was in ballast and bound for Hay Point to load coal. 

Figure 1: Blossom Bank pilot boarding ground and Hydrographers Passage

A chart showing the location of  Blossom Bank pilot boarding ground, Hydrographers Passage, Mackay and Hay Point

Source: Australian Hydrographic Office, annotated by the ATSB

Meanwhile, at Mackay Airport, a twin‑engine Agusta A109E helicopter, operated by Flyon Helicopters and registered VH‑XUM (XUM), with 2 pilots on board, embarked the marine pilot scheduled to conduct the ship’s pilotage. The marine pilot transfer (MPT) flight to Star Coral was the first scheduled for the helicopter and its pilots that day. These flights were normally conducted as a single‑pilot operation. However, on this occasion, the pilot flying, a pilot recently engaged by the operator under its ‘in‑command‑under supervision’ (ICUS)[2] program, was under the supervision of a company check pilot (pilot supervising). 

The pilots’ plan was to transfer Star Coral’s marine pilot and then proceed to a nearby outbound ship to collect its marine pilot for return to Mackay.

At 0759, the helicopter departed Mackay Airport under the control of the pilot flying. En route, the pilots established communication with Star Coral’s master via VHF[3] radio. The master advised that the ship was rolling about 3° on its inbound heading due to a 2 m south‑easterly swell. Subsequently, the pilots requested the master to reposition the ship on a heading[4] of 270° to reduce rolling. At 0853, the pilot flying landed the helicopter on the ship’s helideck, situated on the number 5 cargo hold hatch cover (Figure 2). The marine pilot exited the helicopter and proceeded to the ship’s bridge. 

Figure 2: Landing position of VH-XUM aboard Star Coral

An image showing the helideck location on Star Coral with a separate diagram showing the heading of the helicopter while on the ship, relative to the ship and wind.

This figure is a representation of the helicopter’s orientation relative to the wind during the take‑off. Source: Flyon Helicopters and Star Coral, annotated by the ATSB

Meanwhile, the helicopter remained on the helideck at flight idle[5] while its pilots radioed the outbound ship’s pilot to coordinate the transfer. After some discussion, the pilots elected to keep the helicopter on the deck of Star Coral until the outbound ship had departed the compulsory pilotage area.

After about 5 minutes, as the 2 ships were about to pass each other, the helicopter pilots began conducting their pre‑take‑off checks. The pilots observed a 20 to 28 knot headwind (relative to the helicopter) and noted that the ship was rolling less than 2°. The pilot flying conducted a brief for a performance category 1[6] take‑off, which involved establishing the helicopter in a hover 35 ft above deck height before departing. Both pilots later recalled that everything seemed normal as the take‑off checks were completed. 

At about 0900, the pilot flying raised the collective[7] and observed the engine torques increasing through 50%. The pilot flying recalled the aircraft became light on its oleos as though it was ‘right at the point of lifting off’. Meanwhile, the pilot supervising was observing the outbound ship passingA few seconds later, both pilots felt a sudden and substantial vibration. 

The pilot supervising immediately looked down at the controls and recalled that the pilot flying was holding the cyclic[8] in an abnormally aft position. Concerned that the main rotor might have struck the tail boom, the pilot supervising decided to assume control of the helicopter and took hold of the cyclic and collective unannounced. Meanwhile, the pilot flying was still attempting to lift off, unaware of the pilot supervising’s decision to take control. The pilot supervising recalled that the pilot flying had centred the cyclic and ‘must have’ lowered the collective by the time the pilot supervising took hold of the controls. In contrast, the pilot flying stated that the pilot supervising rapidly lowered the collective after the vibration started, causing the aircraft to descend from being light on its oleos and bounce heavily on the helideck.

Moments later, the cyclic became uncontrollable as the vibrations suddenly worsened into a violent, vertical oscillation of the airframe. The pilot supervising tried to stabilise the helicopter but was unable to control the cyclic movement. Subsequently, the pilot supervising elected to shut down the engines. 

The pilot supervising initially struggled to reach the engine mode switches (located on the centre console) due to the severe vibrations but subsequently managed to shut down engine number 2. The vibrations slightly eased and moments later, they were able to also shut down engine number 1. The vibration dissipated and the helicopter came to rest in an upright position on the helideck, having spun more than 90° counterclockwise from its initial heading. The sequence, from the attempted take‑off to shut‑down occurred within a period of about one minute.

Soon after, the pilots exited the wreckage and inspected the damage. The tail rotor was separated from the helicopter and had come to rest on the main deck between cargo hatches 4 and 5. Items of debris, including main rotor fragments, laid scattered on the deck along with some hydraulic fluid pooled beneath the substantially damaged fuselage (Figure 3).  

Figure 3: Helicopter wreckage 

A photo of the helicopter wreckage on the deck of the bulk carrier, Star Coral

Source: Star Coral

Apart from a thumb sprain to the pilot supervising and some bruising to both pilots’ upper leg areas, where they had been struck by the cyclic, neither were significantly injured and no‑one on board Star Coral was injured.

Context

Helicopter information

The helicopter was an Agusta A109 E variant, manufactured in 2006 and issued serial number 11684. It was registered in Australia in 2006 and began services under the operator’s Air Operator’s Certificate (AOC) in 2023. 

The Agusta A109E is a multipurpose helicopter equipped with 2 Pratt & Whitney PW206‑C turbine engines. It has a fully articulated 4‑blade main rotor system, a 2‑blade tail rotor and retractable tricycle landing gear. Able to carry up to 7 occupants, it has a maximum allowable take‑off weight of 2,850 kg. 

The helicopter was able to perform flight performance class 1 operations by adherence to Category A procedures[9]. While the helicopter was normally operated from the right crew seat, it was fitted with dual controls. A left seat‑approved pilot in command (PIC) was permitted to occupy either seat during training flights. Each set of controls could not be operated independent of the other. 

The helicopter’s wreckage was recovered from the ship 2 days after the incident and transported to a secure hangar at Mackay Airport. Prior to its removal, photographs of the wreckage and the accident area were taken. There were no indications that the main rotor or tail rotor had struck any part of the ship during the accident. 

Based on its inspections, the operator advised that no engine faults or exceedance alarms had been recorded by the helicopter’s electronic engine management systems. Additionally, no faults or defects had been reported by any of XUM’s pilots or maintainers leading up to the occurrence flight. 

Post-accident activities

There was no recorded flight data available to determine the flight control inputs and their effect on the motion of the helicopter during the occurrence.[10] The pilots’ accounts, a witness statement from the master of Star Coral and photographs of the wreckage were the main sources of evidence. 

The ATSB also sought the manufacturer’s input for this occurrence. The manufacturer advised that its preliminary assessment of the available evidence suggested that the helicopter damage appeared consistent with a ground resonance phenomenon (see the section titled Ground resonance).

The licenced maintenance organisation for XUM carried out an examination of the wreckage at the Mackay hangar. On advice from the manufacturer, the examination included inspection of specific components commonly associated with ground resonance. These included main rotor dampers, landing gear struts and tyres. The operator advised the ATSB that the inspection did not identify any airworthiness issues that may have contributed to the occurrence. The operator did not provide the inspection report or findings to the manufacturer for its assessment.

Pilot flying 

The pilot flying obtained a New Zealand commercial helicopter licence (CPL) in 2011 and started flying commercially in 2014. They converted their CPL over to an Australian CPL in 2016 and held a grade 2 flight instructor rating and a class 1 aviation medical certificate. They had experience flying both single and twin-engine helicopters in various operations. Prior to joining the operator’s in‑command‑under‑supervision (ICUS) program in September 2024, they had no previous experience on the A109E, or with marine pilot transfers (MPT). 

Under the ICUS program, the pilot was required to accrue 200 hours on the A109E before they could be assessed to fly the helicopter unsupervised on daytime VFR[11] MPT operations. At the time of the occurrence, the pilot had completed the operator’s training requirements and accrued around 50 hours flight time on the A109E. They had also been cleared to conduct unsupervised MPT operations on single‑engine Eurocopter AS350 helicopters.

Pilot supervising

The pilot supervising was the operator’s head of flying operations and held an air transport pilot (helicopter) licence, issued in 2014, and a class 1 aviation medical certificate. They were approved under the operator’s training and checking system to conduct check and supervision flights on the A109E.

The pilot supervising had been flying helicopters for 26 years in various operations and had accumulated over 10,000 hours flying time, including 3,800 hours in the A109E. They first started MPT operations in 2007 and commenced working with the operator in December 2016.   

Star Coral

Star Coral was built in 2009 by Jansu Newyangzi Shipbuilding, China, registered in The Bahamas and classed with Bureau Veritas. The ship was owned by Panormos Shipping, The Bahamas, and managed and operated by Charterwell Maritime, Greece. 

At the time of the occurrence, the 229 m ship had a mean draught of 6.51 m and the helideck height was about 18 m above the waterline.   

In a written witness statement, the master reported that:

• shortly after the helicopter started to take off, it began to pound on the helideck before it spun and the tail rotor separated

• during the sequence, the helicopter became airborne for no more than 2 seconds.

Ground resonance

Ground resonance can be defined as a vibration of large amplitude resulting from a forced or self‑induced vibration of a helicopter in contact with the ground.[12] The phenomenon is normally associated with helicopters equipped with fully articulated main rotor systems consisting of 3 or more rotor blades. It is more common on helicopters with sprung landing gear than those with skids. Typically, ground resonance occurs during landing, take‑off and ground manoeuvres.[13]

In fully articulated rotor systems, drag hinges allow each blade to advance or lag in the plane of rotation to compensate for the stresses caused by the acceleration and deceleration of the rotor hub. Such rotor systems are typically fitted with lead‑lag dampers to limit the extent of this movement and help prevent excessive vibrations. However, if for any reason one or more of the blades assumes a dragged position different to the others, the blades will move out of phase and the rotor will become imbalanced, transmitting an oscillation throughout the entire airframe.[14]

The risk of ground resonance arises when the unbalanced forces in the rotor system cause the fuselage to oscillate on its landing gear at or near its natural frequency. Ground resonance will occur if the helicopter’s damping systems are unable to compensate for the oscillation.[15] Unless corrective action is taken, the amplitude of the oscillation will increase until the helicopter becomes uncontrollable.[16] Ground resonance can also be induced when the helicopter is in light contact with the ground, if the landing gear oscillation frequency is in sympathy with the rotor head vibration.[17]

Ground resonance is commonly precipitated by the helicopter making hard or asymmetric contact with the ground, landing on a slope or sudden control movements by the pilot.[18] It can also result from other factors such as improper blade balancing and tracking, or damage to any of the blades.[19] Hard contact with the ground by some part of the landing gear when the main rotor is in an unbalanced state can further aggravate the condition.[20]

Additionally, improper maintenance of the helicopter’s main rotor and fuselage damping systems, or incorrect tyre pressures, can induce or worsen ground resonance.[21]

Flight control inputs that may induce ground resonance typically involve sudden control movements or a mishandling of the cyclic that causes the fuselage to bounce.[22]

The helicopter manufacturer advised that the application of certain cyclic commands, such as extreme aft cyclic input, could theoretically reduce the main rotor damper effectiveness in respect to the damping action on the blades’ regressive lead‑lag dynamic.

Recovery technique

The onset of ground resonance can be recognised by a rocking motion or oscillation of the fuselage while on the ground.[23] The United States Federal Aviation Administration (FAA) Helicopter Handbook[24] documented 2 widely accepted recovery techniques: 

• if the condition arises when there is insufficient rotor speed for take‑off, the only option is to lower the collective to reduce the pitch of the blades. The rotor rpm[25] should also be reduced as soon as possible.[26]

• If the rotor speed is in the normal operating range for flight, the Helicopter Handbook recommends lifting the helicopter off the ground to allow the rotor blades to rephase themselves automatically. 

Additionally, the FAA cautioned that:

If a pilot lifts off and allows the helicopter to firmly re‑contact the surface before the blades are realigned, a second shock could move the blades again and aggravate the already unbalanced condition. This could lead to a violent, uncontrollable oscillation.  

In practice, a pilot experiencing ground resonance typically has seconds to identify the condition and take corrective action. 

Similar occurrences

The ATSB reviewed several investigation reports relating to previous A109E accidents attributed to ground resonance. The incidents reviewed occurred outside of Australia between 2006 and 2025 and the contributing factors were found to be operational. Technical factors which may have caused or exacerbated ground resonance were not identified. 

Details of the previous incidents bear similarity to the occurrence involving XUM, particularly in respect to subsequent damage to the helicopter (Figure 4). 

Figure 4: Previous occurrences of ground resonance involving the Agusta A109E

Four separate images showing damaged Agusta A109 helicopters after experiencing ground resonance in previous accidents.

Source: Leonardo Helicopters

Flight manual procedures

The A109E rotorcraft flight manual (RFM) listed fault conditions and corrective actions for emergencies and malfunctions that might occur during take‑off.

The RFM included the caution below for ground resonance within the normal flight procedure for take‑off. This was not part of the emergency and malfunction procedures.

The normal take-off procedure from the helicopter's flight manual

The RFM procedure for ground resonance was consistent with recovery techniques published by the FAA. The RFM reference to the helicopter being ‘free of ground resonance’ was intended to indicate  that, like all helicopters, the A109E was designed and certified to applicable standards so that the rotor and fuselage systems do not vibrate at the same frequency under normal conditions.   

Operator procedures

As an AOC holder, the operator maintained a CASA‑approved[27] operations manual/exposition[28] to promulgate general policy and standardised procedures for MPTs on the A109E. The version of the operations manual current at the time of the occurrence was issued by the operator in November 2023.

Ground resonance

The operator’s normal procedures and emergency checklists for the A109E were derived from the RFM and did not contain any procedures related to ground resonance. 

Crew coordination in response to abnormal situations

While MPT flights were predominantly conducted by a single pilot, the helicopter was certified for operations with either a single pilot or 2 pilots. In either case, the normal procedure and emergency checklists remained the same, except that 2‑pilot checklist procedures were to be based on challenge and response. 

Normal handover and takeover procedures provided that:

In the case where the pilot flying (PF) is not the PIC and the PIC determines that the PF is not maintaining adequate control of the aircraft, the PIC may elect to take control, in which case they will signal their intention by saying ‘I have control’ upon which the PF will immediately relinquish control and the roles will reverse.

In abnormal or emergency situations, the PIC was responsible for ensuring the aircraft was flown and kept under control. The operations manual emphasised the importance of cockpit resource management (CRM) standards throughout the situation, in accordance with the below procedure:

The emergency and abnormal situation procedure from the operations manual

Note: In the above procedures PM stands for ‘pilot monitoring’, NR refers to main rotor speed and IAS means indicated airspeed. 

In the context of rapidly escalating emergencies such as ground resonance, pilots have limited time to perform the procedure. 

Pilot in command responsibility during training flights

As the holder of a certificate that authorised air transport and aerial work operations, the operator was required to have in place a training and checking system (TACS). A training and checking manual (TACM) sets out policies and procedures for conducting training flights. It provided that a check pilot supervising ICUS training was to be the PIC. Check pilots were to ensure that pilots involved in training exercises were made aware of who was acting as the PIC through proper handover of control procedures. 

While an ICUS pilot might be considered the PIC for flight‑time logging purposes, the pilot supervising was deemed the PIC and responsible for the safety of the flight. The TACM stated that in the event of an actual emergency during flight training:

If the flight examiner or check pilot deems it necessary to take physical control of the aircraft at any stage after the occurrence of the emergency, then they shall do so in accordance with the hand‑over and take‑over procedures specified in the Operations Manual - Hand over and take‑over procedures.

The flight examiner or check pilot must be prepared and ready to assume physical control of the aircraft at any stage, particularly during critical manoeuvres such as during take‑off and landing.

As such, beyond the normal handover of control procedures, there were no special provisions in the TACM for the allocation of PIC responsibility and PF duties during ICUS flights. 

Briefings

For 2‑pilot operations or training flights, the operator’s procedures did not require pilots to brief who would assume PF duties in the event of an abnormal or emergency situation during critical phases of flight. 

Operational limits

Under the operator’s operations manual, the A109E was permitted to conduct daytime MPT operations up to a wind strength of 30 knots, with a maximum crosswind of 20 knots. The operational limit for ship’s pitch was 4° up and 2° down while the maximum permissible roll was 4°. The manufacturer did not have input into these operator‑defined limits. 

The pilots reported that the conditions at the time of the occurrence (20‍–‍28 knot headwind, 2° roll and minimal pitching) were within the operator’s limits for MPTs.

Safety analysis

Prior to the accident, VH‑XUM (XUM) made an uneventful landing on Star Coral and remained on the deck for several minutes without incident. There was no evidence that the helicopter was operating abnormally or experienced any instability during this period. 

Examination of the accident site did not reveal any evidence to suggest that the occurrence resulted from the main rotor or tail rotor striking the ship. Star Coral’s master reported that the tail rotor separated after the helicopter started contacting on the deck, indicating that contact with the tail boom by the main rotor was a consequential rather than causative factor. 

In that context, it is most likely that the helicopter encountered ground resonance. Assessment of the damage to the helicopter following the occurrence revealed significant similarities to that seen in previous A109E incidents attributed to this phenomenon. 

It is well established that ground resonance only arises when the helicopter is in contact with the ground. Both pilots asserted that the helicopter did not become airborne prior to the vibrations while the master reported that it became airborne for about 2 seconds. However, it is more likely this occurred after the vibration worsened and the helicopter started rebounding on the helideck. 

The exact cause of the vibration could not be determined. The possibility of causative operational factors such as flight control inputs or environmental factors could not be ruled in or out. 

Similarly, while the operator’s post‑accident inspection of the helicopter (including examination of its rotor and fuselage damping systems) did not reveal any apparent defects, causative technical factors could not be discounted.

However, the sudden lowering of the collective after the onset of the vibration likely aggravated the situation. The helicopter was almost certainly light on its oleos when the vibration began. Therefore, a sudden lowering of the collective would have caused the helicopter to come down firmly on the helideck. The United States Federal Aviation Administration (FAA) Helicopter Handbook describes that such an impact when the rotor is already in an unbalanced state can cause the rotor blades to move further out of phase, resulting in violent uncontrollable oscillations. This description is consistent with the occurrence sequence described by the pilots and the master. 

The pilots’ accounts of who lowered the collective differed. The recollection of the pilot flying that their intention was to lift the helicopter off the deck in response to the vibration was not consistent with a lowering of the collective. In contrast, the pilot supervising did not immediately identify the source of the vibration and later shut down the engines, believing the main rotor may have struck the tail boom. In this context, lowering of the collective would be a natural and expected response. Therefore, it is most likely that the pilot supervising lowered the collective while the pilot flying was attempting to lift the helicopter off the helideck.

In isolation, the immediate responses taken by each pilot following the sudden onset of the significant vibration were understandable. However, since the helicopter’s rotor speed was in the normal operating flight range, continuation of the take‑off would probably have resulted in the vibration dissipating (as detailed in the FAA Helicopter Handbook).

The operator had adequate procedures for responding to abnormal and emergency situations. However, the rapidly escalating nature of this occurrence meant that there was virtually no time to implement them. There was no requirement for the pilots to conduct a pre‑flight or pre‑take‑off brief about who would assume flying duties in the event of an emergency on take‑off. Therefore, the normal procedures for handover and takeover of control were assumed to apply.

However, the time between observing the vibrations and the loss of control severely limited the time available for a formal transfer of control between the pilots. As a result, neither of these procedures were followed and each pilot responded to the situation separately. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the loss of control during marine pilot transfer operations, involving an Agusta A109E, VH‑XUM and bulk carrier Star Coral, about 200 km north‑east of Mackay, Queensland, on 25 February 2025.

Contributing factors

  • During take‑off, the helicopter likely experienced ground resonance, resulting in the rapid onset of significant vertical oscillations through the airframe.
  • Discontinuing the take‑off after the onset of the vibration, with the rotor speed in the flight range, probably resulted in the loss of control and substantial damage to the helicopter.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence. 

Safety action by Flyon Helicopters 

Following this occurrence, the helicopter’s operator, Flyon Helicopters, established ground resonance guidelines for its pilots. Forming part of its exposition, the guidelines were purposed to raise awareness of ground resonance and provide information about how to recognise and respond to the phenomenon. They included response procedures and featured case studies and video resources. The procedures were to be implemented into the operator’s training framework for new and current pilots. 

Flyon Helicopters advised the ATSB that it also planned to implement an additional briefing procedure in its training and checking manual (TACM). The briefing is to be conducted by the training or checking pilot prior to any training or checking flight. It will include:

  • the objectives and scope of the flight, including the intended lesson plan or sequence
  • the training/checking outcomes
  • the roles of each pilot, including the allocation of aircraft command responsibility
  • procedures for transferring aircraft control between pilots
  • actions to be followed in the event of an actual emergency
  • procedures to be used in the simulation of emergencies
  • procedures for the conduct of unusual operations
  • the method to be used to simulate instrument flight conditions, if required
  • human factors/non‑technical stills and threat and error management.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilots and operator of VH-XUM
  • the master and manager of Star Coral
  • the helicopter manufacturer, Leonardo Helicopters

References

Lemmens Y, Troncone E, Dutré S, Olbrechts T. (2012). Identification of Helicopter Ground Resonance with Multi-body Simulation28th International Congress of the Aeronautical Sciences

United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 - Helicopters

Salini S N, Haradev G S, Ranjith M. (2020). Ground Resonance: Nonlinear Modelling and Analysis, 6th Conference on Advances in Control and Optimization of Dynamical Systems (ACODS), India

United States Federal Aviation Administration. (2019). Helicopter Flying Handbook

Schafer J. (1980). Helicopter Maintenance

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the pilots and operator of VH-XUM
  • the master and manager of Star Coral
  • the ship’s flag State administration, The Bahamas
  • the helicopter manufacturer, Leonardo Helicopters
  • Agenzia Nazionale per la Sicurezza del Volo (ANSV)
  • Civil Aviation Safety Authority
  • Australian Maritime Safety Authority 

Submissions were received from:

  • the pilots of VH-XUM
  • the ship’s flag State administration, The Bahamas
  • the helicopter manufacturer, Leonardo Helicopters
  • Agenzia Nazionale per la Sicurezza del Volo (ANSV)

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

 Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Hydrographers Passage provides a deep-water shipping route through the Great Barrier Reef between Blossom Bank pilot boarding ground, near the entrance to the passage, and the Cumberland Islands, north-east of Mackay. Pilotage is compulsory through Hydrographers Passage for ships over 70 m, as well as for loaded oil and chemical tankers and gas carriers, irrespective of size.

[2]     In-command-under-supervision (ICUS) generally refers to a pilot who is acting as the pilot in command (PIC) for a flight under the supervision of a more experienced pilot.

[3]     Very high frequency.

[4]     All ship’s headings are reported in degrees true. 

[5]     Flight idle refers to the lowest engine power setting that allows the aircraft to maintain stable operations during flight. A flight idle setting when the helicopter is on the ground allows for the engine(s) to go to higher power settings faster and facilitate take-off when collective pitch is raised. 

[6]     Performance Class 1 (PC1) refers to operations for which, in the event of a critical engine failure, performance is available to enable the helicopter to safely continue the flight to an appropriate landing area.

[7]     Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical speed.

[8]     Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.

[9]     Category A (CAT A) operations were those where, in the event of an engine failure, the helicopter has adequate performance to safely continue or reject the take-off or landing.

[10]    The aircraft type involved was not required under regulations to carry a cockpit voice recorder (CVR) or flight data recorder (FDR). 

[11]    Visual flight rules.

[12]    United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 – Helicopters. 

[13]    Lemmens Y, Troncone E, Dutré S, Olbrechts T. (2012). Identification of Helicopter Ground Resonance with Multi-body Simulation, 28th International Congress of the Aeronautical Sciences.

[14]    United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 – Helicopters.

[15]    Salini S N, Haradev G S, Ranjith M. (2020). Ground Resonance: Nonlinear Modelling and Analysis, 6th Conference on Advances in Control and Optimization of Dynamical Systems (ACODS), India.

[16]    United States Federal Aviation Administration. (2019). Helicopter Flying Handbook. 

[17]    United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 – Helicopters.

[18]    ibid.

[19]    ibid.

[20]    United States Federal Aviation Administration. Helicopter Flying Handbook, 2019.

[21]    Schafer J. Helicopter Maintenance, 1980.

[22]    United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 – Helicopters.

[23]    United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 – Helicopters.

[24]    United States Federal Aviation Administration. Helicopter Flying Handbook, 2019.

[25]    Revolutions per minute. 

[26]    United Kingdom Ministry of Defence, AP3456 Central Flying School Manual of Flying Vol 12 – Helicopters.

[27]    Civil Aviation Safety Authority.

[28]    ‘Exposition’ is a term used in some regulatory domains for a document or set of documents that describe how an organisation will comply with all applicable legislative requirements, and how they will manage the safety of their operations. An exposition is broadly equivalent to an operations manual in other domains.

Occurrence summary

Investigation number AO-2025-009
Occurrence date 25/02/2025
Location 200 km north-east of Mackay
State Queensland
Report release date 29/07/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Loss of control
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Agusta, S.p.A, Construzioni Aeronautiche
Model A109E
Registration VH-XUM
Serial number 11684
Sector Helicopter
Operation type Part 138 Aerial work operations
Departure point Mackay Airport, Queensland
Destination Mackay Airport, Queensland
Damage Substantial

Ship details

Name Star Coral
IMO number 9477854
Flag The Bahamas
Departure point Tianjin, China
Destination Hay Point, Queensland

Airframe overspeed involving Diamond DA40, VH-EQF, 63 km east of Kingaroy Airport, Queensland, on 12 February 2025

Final report

Report release date: 06/06/2025

Investigation summary

What happened

At 1520 on 12 February 2025, an instructor and student departed from Brisbane West Wellcamp Airport, Queensland for a training flight in a Diamond DA40 aircraft, registered VH-EQF and operated by Flight Training Adelaide.

At 1649, as the instructor and student were conducting stall and upset recovery training at an altitude of about 6,300 ft above mean sea level, the instructor took control of the aircraft. Acting on impulse and without providing a briefing to the student, the instructor attempted a wingover.

During the attempted wingover, the bank angle quickly exceeded the aircraft’s 60° bank angle limitation before continuing beyond inverted and the aircraft’s pitch became steeply nose down. During the recovery, the speed increased beyond the aircraft’s never exceed airspeed (VNE). The flight was completed without further incident and the aircraft landed at Wellcamp at 1726.

What the ATSB found

The ATSB found that the instructor attempted a wingover manoeuvre for which they had not been trained. During the manoeuvre, the aircraft was rolled through 360°, exceeding the aircraft's 60° bank angle limit and the aircraft exceeded VNE by 20 knots.

What has been done as a result

Following the incident, Flight Training Adelaide issued an internal notice to instructors and students restricting the conduct of non-training syllabus manoeuvres. The notice advised that prior to such manoeuvres being conducted, prior permission must be obtained from the Head of Operations or Deputy Head of Operations.

A presentation was also provided to instructors on the importance of personal limitations and effective decision‑making to ensure safe operations.

Safety message

This incident underlines that pilots should not attempt unfamiliar manoeuvres without first receiving appropriate training. Effective training reduces the likelihood of mishandling and also prepares a pilot to respond appropriately should a manoeuvre deviate from the intended flightpath.

While the aircraft was not damaged during this incident, it is important that all exceeded limitations are entered onto the maintenance release and reported quickly to ensure the aircraft is inspected before further flight. This will ensure that other pilots are not exposed to the risk of operating a damaged aircraft.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

At 1520 local time on 12 February 2025, an instructor and student departed from Brisbane West Wellcamp Airport, Queensland for a training flight in a Diamond DA40 aircraft, registered VH-EQF and operated by Flight Training Adelaide. The flight intended to track via Gatton and Sunshine Coast Airport before conducting stall and upset recovery training near Jimna and then returning to Brisbane West Wellcamp Airport (Figure 1).

Figure 1: Overview of flight

A satellite image of the area of the flight overlaid with the recorded flightpath. The turning points for the flight are annotated.

Source: Google Earth, annotated by the ATSB 

At 1649, as the instructor and student were conducting the stall and upset recovery training at an altitude of about 6,300 ft above mean sea level (AMSL), the instructor took control of the aircraft. Acting on impulse, and without providing a briefing to the student, the instructor attempted a wingover manoeuvre (see the section titled Wingover). The instructor pitched the aircraft down to increase speed before pitching the aircraft up and beginning a rapid left roll at 120 kt indicated airspeed. At the same time, the instructor began reducing engine power.

The roll quickly exceeded the aircraft’s 60° bank angle limitation (see the section titled Aircraft details) and the instructor continued applying a roll input. As the roll angle exceeded 90°, the pitch angle dropped below the level attitude and the airspeed began increasing. The aircraft then rolled beyond inverted, the aircraft’s pitch became steeply nose down, and the instructor reduced power to idle to begin recovery from the dive. 

The instructor was aware of the risk of exceeding the aircraft’s maximum G[1] limitation and so slowly increased the pitch attitude as speed continued increasing. At 1649:56, the speed increased beyond the never exceed speed[2] of 178 kt, and 3 seconds later reached a maximum of 198 kt. The instructor continued the recovery from the dive and at 1650:02, the aircraft reached a minimum recorded altitude of 4,159 ft AMSL before a climb was commenced. At 1650:04, the speed reduced below 178 kt.

The instructor then climbed the aircraft back up to an altitude of about 5,000 ft and the student advised the instructor of the speed exceeding 178 kt. The instructor then conducted an inspection of the airframe visible from the cabin and did not identify any defects. They then handed control of the aircraft back to the student to continue the flight. About 3 minutes after the incident, another stall recovery training manoeuvre was completed. The rest of the flight was conducted normally, with the student flying the aircraft. At 1726 the aircraft landed at Wellcamp.

The instructor reported that, after landing, they thought about the attempted wingover, but also had to focus on preparation for another flight. The instructor confirmed that no bookings were scheduled for the aircraft that evening, however they did not mark the aircraft as unavailable or endorse its maintenance release at that time. The instructor then completed an evening of night flying in another aircraft. Later at home they recognised that the incident needed to be reported to the operator and intended to do so the next morning.

Early the next morning, the instructor marked the aircraft as unserviceable in the operator’s booking system. The instructor also contacted the operator’s training manager and had the aircraft’s maintenance release endorsed to prevent further flights.

Context

Instructor and student details

The instructor held a commercial pilot licence (aeroplane) and class 1 aviation medical certificate. The instructor had 930 hours of flying experience, of which 900 hours were in the DA40, with 120 hours accrued in the previous 90 days. 

The instructor had completed spin recovery training but had not completed any other aerobatics training and did not hold an aerobatics endorsement. The instructor had previously been in a DA40 where a wingover had been demonstrated, but the instructor had not received training in conduct of the manoeuvre.

The student held a student pilot licence (aeroplane) and class 1 aviation medical certificate and had about 125 hours of flying experience.

The ATSB found no indicators that the instructor or student were experiencing a level of fatigue known to adversely affect performance.

Aircraft details

The Diamond Aircraft Industries DA40 is a 4-seat, low-wing, fixed-tricycle-undercarriage aircraft with a single reciprocating engine driving a variable pitch 2-bladed propeller (Figure 2). The never exceed speed (VNE) of 178 kt was not to be exceeded for any operation in the aircraft.

Figure 2: VH-EQF

Figure 2: VH-EQF

Source: Mitch Coad, modified by ATSB

The DA40 was certified to operate in the normal and utility categories and was not certified for aerobatics. The utility category had a maximum weight limit of 980 kg. For all operations above that weight, the aircraft could be operated in the normal category only. At the time of the incident, the aircraft weighed 1,111 kg. 

The aircraft’s airplane flight manual stated that when operated in the normal category, the maximum positive load factor was 3.8 G and approved manoeuvres were limited to:

1) All normal flight manoeuvres;

2) Stalling (with the exception of dynamic stalling); and

3) Lazy Eights, Chandelles, as well as steep turns and similar manoeuvres, in which an angle of bank of not more than 60° is attained.

The manual also cautioned that aerobatics, spinning, and flight manoeuvres with more than 60° of bank were not permitted when operating in the normal category. When operating the aircraft in the utility category, the bank angle limitation was 90°. All other manoeuvre limitations were unchanged.

Wingover

The wingover manoeuvre involves a combination of pitching up and banking of the aircraft to effect a change in heading. It can be conducted at varying angles of bank and pitch to turn through different angles of heading change. For a typical 180° heading change wingover, the aircraft is descended slightly to accelerate before the aircraft is pitched up to commence a climb, followed by a left or right turn. During the turn, the pitch is reduced below level to commence descending. The angle of bank is then reduced to exit the manoeuvre in the opposite direction, at the same altitude as commencement and with wings level.

A lazy eight is a pair of wingovers of 180° heading change made in succession and in opposite directions. The resulting flightpath resembles a horizontal figure of 8 (Figure 3).

Figure 3: Lazy eight manoeuvre

A pictorial representation of the lazy 8 manoeuvre.

Source: United States Federal Aviation Administration Airplane Flying Handbook

Aerobatics

The Civil Aviation Safety Authority defined aerobatics as:[3]

aerobatic manoeuvres, for an aircraft, means manoeuvres of the aircraft that involve:

 (a) bank angles that are greater than 60°; or

 (b) pitch angles that are greater than 45°, or are otherwise abnormal to the aircraft type; or

 (c) abrupt changes of speed, direction, angle of bank or angle of pitch.

Incident reporting and post-incident inspection

Following the flight, the instructor identified that the aircraft was not scheduled to be used further that evening. However, the aircraft’s maintenance release was not endorsed, and the aircraft was not made unavailable until early the following morning. 

Upon being advised of the exceedance, the aircraft manufacturer required that the aircraft undergo a minimum of a major structural inspection. This inspection found that the aircraft was not damaged during the incident. 

Meteorology and terrain

The incident manoeuvre was conducted in clear visual meteorological conditions. 

At 1700, 11 minutes after the incident, the Bureau of Meteorology (BoM) automatic weather station at Kingaroy Airport, 63 km west of the incident recorded the wind as 4 kt from 060° magnetic. There was no recorded cloud and visibility was greater than 10 km.

The ground level elevation beneath the aircraft during the incident was about 1,400 to 1,650 ft AMSL.

Recorded data

The aircraft was equipped with Garmin G1000 instrumentation that recorded the incident (Figure 4).

Figure 4: Recorded data from VH-EQF

Figure 4: Recorded data from VH-EQF

Altitudes are above mean sea level. Source: ATSB

The manoeuvre commenced at 1649:29 with a slight descent and acceleration from an altitude of 6,297 ft AMSL. The left roll then commenced at 1649:47 at an airspeed of 120 kt, a pitch angle of 11° nose up and the bank angle reached 79° left one second later. At the same time engine power began reducing. 

A second later, at 1649:49, the pitch attitude reduced below the level attitude and the bank angle reached 111° left before the aircraft rolled beyond inverted (180° roll) 2 seconds later. At that time, the pitch angle was 33° nose down and the engine power was reduced to idle as the aircraft accelerated through 122 kt.

At 1649:53, 6 seconds after the roll commenced, the aircraft had rolled through 271° and was now in a right 89° bank, and the pitch angle had reached 59° nose down, with the speed rapidly increasing past 149 kt. Three seconds later, the speed increased beyond the never exceed speed (VNE) of 178 kt and continued increasing. At 1649:56, with the nose still pitched down 19° and the wings now level, the speed reached a maximum of 198 kt. At the same time, the recorded G level increased to a maximum of 1.42 G. Speed then began to reduce and 3 seconds later, the aircraft reached a minimum recorded altitude of 4,159 ft AMSL, about 2,600 ft above the ground. Another 5 seconds later, at 1650:04, the speed reduced back below VNE.

Safety analysis

During stall and upset recovery training, the instructor took control of the aircraft and, without briefing the student, attempted a wingover. A wingover, being essentially half of a lazy eight, was a permitted manoeuvre in the aircraft provided the angle of bank did not exceed 60° (flight manual limitation) and the pitch angle remained less than 45° (aerobatic definition limitation). However, the instructor had not been trained in this manoeuvre and did not increase pitch sufficiently before applying a rapid roll input that quickly exceeded the aircraft’s bank angle limitation. As the aircraft rolled, it began pitching down rapidly and as the roll passed beyond inverted, the pitch angle became steeply nose down. 

The instructor responded to the nose down attitude by reducing power to idle but then prioritised minimising G load during the recovery from the dive. Although the instructor achieved this aim, with a maximum recorded G value of 1.42 G, well below the 3.8 G maximum, by not increasing pitch more positively, the aircraft’s speed increased rapidly and significantly exceeded the never exceed speed. Exceeding this limitation risked structural damage or failure.

The instructor then recovered from the incident and re-established normal flight before then conducting a visual inspection of the visible airframe. Control was then handed back to the student and a further stall recovery exercise was conducted. The continuation of the planned flight indicated that the risk associated with the incident and the potential for undetected damage and control issues was not fully recognised. However, the aircraft landed without further incident.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the airframe overspeed involving Diamond DA 40, VH-EQF, 63 km east of Kingaroy Airport, Queensland on 12 February 2025.

Contributing factors

  • During a training flight, the instructor attempted a wingover manoeuvre for which they had not been trained.
  • During the manoeuvre, the aircraft pitched steeply nose down and was rolled through 360°, exceeding the aircraft's 60° bank angle limit. During the subsequent recovery, the aircraft exceeded its never exceed airspeed by 20 knots.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence

Proactive safety action by Flight Training Adelaide

Action number:AO-2025-007-PSA-01
Action organisation:Flight Training Adelaide

Flight Training Adelaide issued an internal notice to instructors and students restricting the conduct of non-training syllabus manoeuvres. The notice advised that prior to such manoeuvres being conducted, prior permission must be obtained from the Head of Operations or Deputy Head of Operations.

A presentation was also provided to instructors on the importance of personal limitations and effective decision‑making to ensure safe operations.


Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the instructor and student
  • Flight Training Adelaide
  • Civil Aviation Safety Authority
  • the aircraft manufacturer
  • recorded data from VH-EQF. 

References

United States Federal Aviation Administration (2021), Airplane Flying Handbook (FAA-H-8083-3C) Chapter 10 (p.10-6).

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • Flight Training Adelaide
  • the instructor and student
  • Civil Aviation Safety Authority

Submissions were received from:

  • Flight Training Adelaide
  • the instructor and student

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.


[1]      G load: the nominal value for acceleration. In flight, G load represents the combined effects of flight manoeuvring loads and turbulence and can have a positive or negative value.

[2]      VNE (Never Exceed Speed): the speed limit that may not be exceeded at any time. The calculation of this speed is driven by structural or aerodynamic limitations; however, control system flutter is typically one limitation that factors heavily into the calculation of VNE.

[3]      Civil Aviation Safety Regulations Part 91 – Dictionary, Part 1 - Definitions

Occurrence summary

Investigation number AO-2025-007
Occurrence date 12/02/2025
Location 63 km east of Kingaroy Airport
State Queensland
Report release date 06/06/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Airframe overspeed, Loss of control
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Diamond Aircraft Industries
Model DA40
Registration VH-EQF
Serial number 40.806
Aircraft operator Flight Training Adelaide Pty Ltd
Sector Piston
Operation type Part 142 Integrated and multi-crew pilot flight training
Departure point Brisbane West Wellcamp Airport, Queensland
Destination Brisbane West Wellcamp Airport, Queensland
Damage Nil

Loss of control involving Robinson R22 Beta, near Brunette Downs Station, Northern Territory, on 24 January 2025

Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified. 

What happened

On 24 January 2025, at about 1338 local time, the pilot of a Robinson R22 helicopter was conducting cattle‑mustering operations near Brunette Downs Station, Northern Territory. The pilot was the sole occupant onboard and the helicopter’s doors had been removed. Weather conditions were clear, with a temperature of about 38°C. During mustering, the pilot landed in the open flat ground behind the cattle to rehydrate. The collective[1] was in the full down position while the engine remained at 100% RPM and the pilot held the cyclic[2] between their legs with no flight control frictions engaged.

As the pilot took a sip from their water bottle, they felt the helicopter shake. They then put the bottle down, but the left skid was at this point already a few inches off the ground. They then tried to correct the tilt with left cyclic and reached for the collective, but the helicopter continued to roll to the right. When the helicopter rolled through about 45 degrees the pilot attempted to stop the roll by placing their right foot outside the helicopter and pushing against the ground. The main rotor then contacted the ground, followed by the engine stopping and the aircraft coming to rest on its right side (Figure 1), with the pilot’s right foot trapped underneath the fuselage.

Figure 1: The occurrence R22 helicopter

Figure 1: The occurrence R22 helicopter

Source: Operator supplied              

The pilot was able to extricate their foot out from underneath the helicopter, closed the fuel mixture control and switched off the battery master as they exited.

The helicopter was substantially damaged in the accident, with damage to the right skid, fuselage, main rotor assembly, drive belts, fuel tanks and gearbox.

Safety action

The operator has published a notice to its pilots reminding them to take the following precautions on each landing, no matter how short the time on the ground:

  • Make sure all parts of the skids are firmly on the ground and the helicopter is stable.
  • Collective set full down, governor off, engine RPM back to idle or 75%, cyclic neutral with friction on. Collective strap or friction always applied when the helicopter is on the ground and keep feet on the pedals.
  • Be aware of possible dust devils[3] in the area, these may be hard to see in the wet season as there is no dust or grass present to indicate their location.
  • Pilots are to report any cases where the collective rises on its own so any potential technical issues can be investigated and corrected.

Safety message

Helicopter pilots conducting mustering operations will be regularly landing for short periods of time for various reasons, including rehydration. Good airmanship requires that the helicopter is in a safe and stable condition before releasing the controls, including reducing RPM to idle and making sure the collective is in the full down position with the control frictions applied. This will reduce the risk of the helicopter inadvertently becoming airborne in case of disturbances from environmental conditions.

Once started, dynamic rollover will develop quickly and cannot be stopped by application of opposite cyclic control alone. Even with full opposite cyclic applied, there is insufficient control authority to arrest the roll once it is developed, as the main rotor thrust vector and its moment arm serves to accelerate the roll. Quickly reducing collective pitch is the most effective way to stop dynamic rollover from developing.

The R22 Pilot's Operating Handbook includes a safety notice (SN-9) which provides advice about how to avoid dynamic rollover situations.

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

[1]     Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.

[2]     Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.

[3]     Dust devils are visible as wind vortices lifting dust from the surface with diameters usually less than one hundred metres but can extend up to a few thousand feet. They are a common occurrence throughout inland Australia, especially during the warmer months, and are dangerous to aircraft during take-off and landing (Source: Bureau of Meteorology)

Occurrence summary

Mode of transport Aviation
Occurrence ID AB-2025-005
Occurrence date 24/01/2025
Location Near Brunette Downs Station
State Northern Territory
Occurrence class Accident
Aviation occurrence category Loss of control
Highest injury level Minor
Brief release date 17/02/2025

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22 Beta
Sector Helicopter
Operation type Part 138 Aerial work operations
Departure point Brunette Downs Aircraft Landing Area, NT
Destination Brunette Downs Aircraft Landing Area, NT
Damage Substantial

Loss of control and collision with terrain involving Aérospatiale (Airbus Helicopters) AS332L1, N368EV, 41 km north-north-west of Hay Aerodrome, New South Wales, on 22 November 2024

Summary

The ATSB is investigating an accident involving an Airbus Helicopters AS332L1, registration N368EV, 41 km north-north-west of Hay aerodrome, New South Wales, on 22 November 2024. 

The aircraft was conducting a ferry flight from Broken Hill to Albury when it collided with terrain. One crew member sustained fatal injuries and the other sustained serious injuries.

The ATSB released a preliminary report, which details factual information established in the investigation’s early evidence collection phase, on 28 January 2025. See below.

The final report has been drafted and is undergoing internal review to ensure the report adequately and accurately reflects the evidence collected, analysis, and agreed findings.

The final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.

Last updated:

Preliminary report

Report release date: 28/01/2025

This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003

The occurrence

On 22 November 2024, at about 0828 local time, an Aérospatiale (Airbus Helicopters) AS332L1 Super Puma helicopter, registered N368EV, departed Broken Hill Airport, New South Wales for Albury with one pilot and a passenger on board. The flight was the final leg of a repositioning flight from Kuala Lumpur, Malaysia that started on 17 November 2024. The helicopter was being positioned at Albury for use as an aerial firefighting asset over the summer period.

At about 0955, while cruising at about 3,500 ft above mean sea level, the pilot noted a high frequency vibration through the airframe that was also apparent to the passenger. In response, the pilot lowered the collective control[1] and began a descent, noting that Hay aerodrome was about 22 NM (41 km) from their location. Recorded data showed the helicopter was descended at about 1,500 ft/min with an indicated airspeed of about 115 kt.

In interview with the ATSB, the pilot reported that, during the descent, they heard a loud thud, which was immediately followed by an uncommanded yaw[2] to the left. To control the yaw, the pilot established an autorotation[3] then indicated that they reduced the throttles to idle, however, inadvertently reduced the no 2 engine throttle beyond the idle gate position resulting in the engine shutting down. 

With the reduction in power, the uncommanded yaw ceased, and the pilot initiated a straight-in approach towards the open fields below. On approaching the ground, the pilot reported that, during the final flare with reduced airspeed, application of the collective control[4] to cushion the landing resulted in the helicopter yawing again. 

At about 0958, the helicopter landed heavily, initially impacting terrain in an upright attitude but facing in the opposite direction of flight, before rolling onto its right side. The emergency locator transmitter was activated in the impact and there was no post-impact fire. The pilot and passenger survived the impact but were seriously injured. The passenger, who was seated in the forward cabin, succumbed to their injuries. The helicopter was destroyed. 

Context

Pilot information

The pilot held a United States Department of Transportation - Federal Aviation Administration  Airline Transport Pilot Certificate (issued in 2023), with the necessary ratings to fly the helicopter. The pilot also held a Medical Certificate First Class, issued in November 2024.  The pilot also held an Australian-issued Commercial Pilot Licence (issued 2016) with an AS322 type rating.

The pilot completed AS332 type rating training in April 2023 and had about 8,000 hours total aeronautical experience at that time. Since completing the training, the pilot had logged about 400 hours flight time on the AS332. The pilot reported completing annual recurrent training on the AS332 in May 2024.

Helicopter information

General information

The AS332L1 Super Puma is a utility helicopter developed and initially produced by Aérospatiale, and subsequently manufactured by successor companies Eurocopter and Airbus Helicopters. N368EV was manufactured in 1988 by Aérospatiale with the serial number 2179. The helicopter was fitted with 2 Turbomeca Makila 1A1 turboshaft engines. 

The helicopter was registered in the United States and was issued a Certificate of Airworthiness by the Department of Transportation - Federal Aviation Administration in the transport category on 26 January 2011. The type certificate holder was Airbus Helicopters.

At the time of the accident, the helicopter had accrued about 28,323 hours total time in service. 

Tail rotor system

The AS332 tail rotor system comprises a 5-bladed tail rotor assembly that rotates in a counter‑clockwise direction. The tail rotor blades mount to the tail rotor hub and are driven by the tail gearbox via the inclined tail rotor shaft. 

Tail rotor blade pitch control occurs in response to the pilot’s tail rotor pedal inputs via mechanical connection to the servo control. The servo control actuates a pitch change control rod located within the hollow tail rotor shaft and is connected to the pitch change control plate. The pitch change control plate is mounted to and supported by a splined sleeve that slides laterally in a guide located within the tail rotor shaft (Figure 1 and Figure 2).

Figure 1: Tail rotor gearbox and related components

Figure 1: Tail rotor gearbox and related components

Source: Airbus Helicopters, annotated by the ATSB

Meteorological information

The Bureau of Meteorology’s forecast conditions for Broken Hill and Albury airports were described as CAVOK[5] for the duration of the flight. Recorded weather observations for Hay aerodrome showed the mean wind speed varying between 12 kt and 15 kt from the north around the time of the accident.  

The pilot reported that, following the departure from Broken Hill, and while cruising at about 3,500 ft, they were experiencing smooth flying conditions and had a tailwind of about 10⁠–⁠15 kt. 

Recorded data

The helicopter was not fitted with a cockpit voice recorder or flight data recorder. A recent modification included the installation of a helicopter usage and monitoring system from which preliminary flight data was extracted by the ATSB.            

The helicopter was also equipped with a Tracplus RockAIR portable tracking device. Additional navigational equipment was retained for further examination.

Wreckage and impact information

The helicopter impacted grass covered, flat terrain, in a slight left side down, but generally upright attitude facing about 320° (magnetic). The fuselage and belly sections were heavily compressed during the impact sequence, with the aft fuselage structure collapsing, resulting in the tail boom striking the ground. The tail boom ground strike then resulted in the vertical fin, with the tail gearbox and horizontal stabiliser attached, to separate from the tail boom. Following the ground contact and compression damage to the fuselage and tail boom, the helicopter rolled onto its right side. The wreckage was contained within the immediate area of the impact point and minimal forward projection of debris was noted. 

The landing gear was found in the down position with the nose and left main gear sustaining significant damage. The compression of the belly resulted in considerable release of fuel from the fuselage belly tanks. The cabin‑fitted ferry fuel tanks were dislodged from the floor mounts in the impact but remained intact.

During the impact sequence, fractures occurred on the main and tail rotor systems, including an associated loss of blade material consistent with a ground strike. However, each of the blades remained securely attached to their respective attachment point.

Examination of the wreckage found that the tail rotor pitch change control plate was detached from the tail rotor gearbox assembly and was the likely reason for the uncommanded yaw. Closer examination showed that the splined sleeve supporting the pitch change control plate had fractured at the mounting flange and the pitch change control rod was also fractured (Figure 2).

Figure 2: Tail rotor assembly with separation of pitch change control plate from gearbox

Figure 2: Tail rotor assembly with separation of pitch change control plate from gearbox

Source: ATSB

Component examination

Introduction

The fractured splined sleeve was examined at the ATSB’s technical facilities in Canberra, in the presence of representatives from the French Bureau d'Enquêtes et d'Analyses and Airbus Helicopters. 

The manufacturer advised that the splined sleeve had no safe life limit,[6] and its serviceability was determined by on-condition maintenance requirements. The continuation in service of the component was contingent on the absence of corrosion or surface scratches as determined by visual inspection at specified intervals. 

Component examination 

Following the removal of its surface protective coating, the splined sleeve was identified as part number AS332A33 0070.20. The sleeve’s serial number was also identified to assist with determining the component manufacturing history. 

Initial examinations of the fracture surface found that a fatigue crack had propagated around the majority of the splined sleeve’s circumference, leading to fracture of the sleeve in the section adjacent to the pitch change control plate mount flange. Further examination is to be conducted to determine the crack origin and identify the factors contributing to the cracking (Figure 3).

Figure 3: Separation of the pitch change control plate mount flange from the splined sleeve

Figure 3: Separation of the pitch change control plate mount flange from the splined sleeve

Source: ATSB

Safety action

In response to this accident, Airbus Helicopters published safety related information, which included:

  • Safety Information Notice 4082-S-64 on 29 November 2024 that highlighted tail rotor assembly maintenance tasks, specific to inspection and lubrication requirements.
  • Alert Service Bulletin ASB AS332-64-20-003 on 23 December 2024 that specified an inspection for defects of the splined sleeve radius area of the control plate mount flange.

Further investigation

To date, the ATSB has:

  • examined the wreckage
  • collected items of evidence from the accident site
  • collected pilot and aircraft records
  • conducted interviews with relevant parties
  • liaised with Airbus Helicopters and the French Bureau d'Enquêtes et d'Analyses 
  • conducted a preliminary examination of the splined sleeve.

The investigation is continuing and will include:

  • a further review and detailed examination of the splined sleeve
  • examination of the tail gearbox and components
  • an assessment of accident survivability aspects
  • a review of helicopter records and loading aspects 
  • a review of the pilot’s qualifications and experience
  • analysis of recorded data.

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken. 


Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity. Raising or lowering the collective also increases or decreases engine power to maintain rotor RPM as the rotor drag changes.

[2]     Yawing: the motion of an aircraft about its vertical or normal axis.

[3]     Autorotation: Autorotation is a condition of descending flight where, following engine failure or deliberate disengagement, the rotor blades are driven solely by aerodynamic forces resulting from rate of descent airflow through the rotor. The rate of descent determined mainly by airspeed.

[5]     Ceiling and visibility okay (CAVOK): visibility, cloud and present weather are better than prescribed conditions. For an aerodrome weather report, those conditions are visibility 10 km or more, no significant cloud below 5,000 ft, no cumulonimbus cloud and no significant weather.

[6]     Safe life limit: An airworthiness limitation that is applied to life limited parts, which have a predetermined lifespan after which they must be replaced to ensure safety.

Occurrence summary

Investigation number AO-2024-060
Occurrence date 22/11/2024
Occurrence time and timezone 11:45 Australian Eastern Daylight Time
Location 41 km north-north-west of Hay Aerodrome
State New South Wales
Report release date 28/01/2025
Report status Preliminary
Anticipated completion Q4 2026
Investigation level Short
Investigation type Occurrence Investigation
Investigation phase Final report: Internal review
Investigation status Active
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Loss of control, Transmission and gearbox
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Aerospatiale Industries
Model AS332L1
Registration N368EV
Serial number 2179
Aircraft operator Forest Air Helicopters (Aust) Pty Ltd
Sector Helicopter
Operation type Part 91 General operating and flight rules
Activity General aviation / Recreational-Other general aviation flying-Ferry flights
Departure point Broken Hill Airport, New South Wales
Destination Albury, New South Wales
Injuries Crew - 1 (serious), Passengers - 1 (fatal)
Damage Substantial