The ATSB is investigating a fuel starvation event and forced landing involving a Cessna 207, registered VH-UBW, 6.5 km north of Darwin Airport, Northern Territory, on 24 June 2026.
During the flight, the engine failed, reportedly due to fuel exhaustion, and the pilot conducted a forced landing on a beach.
To date, the ATSB investigation has included:
interviewing the flight crew
examination of maintenance records
analysis of flight data and air traffic surveillance data
operational documentation
pilot records
fuel documentation
air traffic surveillance data and audio recordings.
The final report has been drafted and is undergoing internal review to ensure the report adequately and accurately reflects the evidence collected, analysis, and agreed findings.
The final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.
Last updated:
Occurrence summary
Investigation number
AO-2026-084
Occurrence date
24/06/2026
Occurrence time and timezone
1620 Australian Central Standard Time
Location
6.5 km north of Darwin Airport
State
Northern Territory
Report status
Pending
Anticipated completion
Q4 2026
Investigation level
Short
Investigation type
Occurrence Investigation
Investigation phase
Final report: Internal review
Investigation status
Active
Mode of transport
Aviation
Aviation occurrence category
Forced/precautionary landing, Fuel starvation
Occurrence class
Serious Incident
Highest injury level
None
Aircraft details
Manufacturer
Cessna Aircraft Company
Model
207
Registration
VH-UBW
Serial number
20700137
Aircraft operator
Air Frontier Pty Ltd
Sector
Piston
Operation type
Part 135 Air transport operations - smaller aeroplanes
Activity
Commercial air transport-Non-scheduled-Passenger transport charters
On the morning of 1 May 2026, a Piper PA-32R-301 Saratoga, registered VH-LPW, departed Essendon for a flight to Stawell, Victoria, with a pilot and 2 allied health clinician passengers on board.
The aircraft flew to Stawell, Victoria, disembarked a clinician, then flew to Horsham, Victoria, where the second clinician disembarked. The pilot operated the flights to Horsham using the left wing fuel tank and intended to change to the right tank to operate the return flights. Later in the day, after the clinician had attended to their appointments, the aircraft departed Horsham before collecting the second clinician from Stawell and departing with both on board for the return to Essendon.
At 1616, as the aircraft was cruising at 7,000 ft above mean sea level, the engine began to run rough. In response, the pilot commenced the engine power loss in flight actions which included selecting the right fuel tank. After switching to the right fuel tank, normal engine power did not immediately return, and the pilot assessed that the rough running was not fuel‑related. The pilot then shut the engine down and completed a power-off landing at the nearby Bacchus Marsh Aerodrome.
What the ATSB found
The ATSB found that the planned fuel tank change at Horsham before the return flights was inadvertently omitted. This omission was not detected prior to the contents of the left fuel tank being exhausted and the engine began running rough.
In response to the rough running, the appropriate emergency actions were not fully completed, and the engine was shut down before those actions could take effect. This resulted in an unnecessary increase in safety risk associated with the power-off forced landing.
Safety message
Accidents involving fuel mismanagement are an ongoing aviation safety concern and are a reminder of the importance of monitoring fuel levels prior to, and during, flight. Adhering to procedures, maintaining an accurate fuel record, and ensuring appropriate tank selections are made for the phase of flight will lessen the likelihood of fuel starvation and/or fuel exhaustion.
This incident also highlights the importance of careful and methodical emergency response actions. In this case the engine failure response actions were not fully completed, resulting in power not being restored to an otherwise serviceable engine.
The investigation
The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
At 0657 local time on the morning of 1 May 2026, a Piper PA-32R-301 Saratoga, registered VH-LPW, departed Moorabbin Airport for a flight to Essendon Airport, Victoria, with the pilot on board. The aircraft was loaded with a total of 323 litres (L) of usable fuel with the left tank full (193 L), while the right tank held 130 L. The flight departed with the left fuel tank selected and landed at Essendon 18 minutes later, where 2 allied health clinicians boarded the aircraft.
From Essendon, the plan was to fly to Stawell, Victoria, to disembark a clinician, then fly on to Horsham, Victoria, where the second clinician would disembark. Later in the day, after the clinician had attended to their appointments, the aircraft would depart Horsham with the pilot and clinician on board before collecting the second clinician from Stawell and returning both to Essendon. Following this, the pilot would return to Moorabbin to conclude the day.
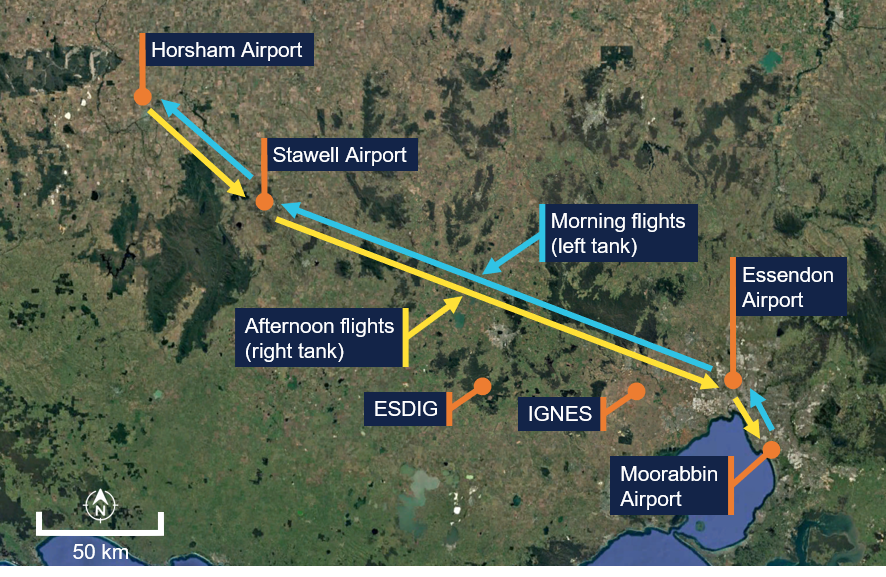
The flights were operated as private flights (see the section titled Operation) under the instrument flight rules.1 The pilot intended to operate the flights to Horsham using the fuel contained in the left tank and then change to the right tank to operate the return flights (Figure 1).
Figure 1: Planned flights
Source: Google Earth, annotated by the ATSB
After completing the morning’s flights, the aircraft landed at Horsham at 0913 with about 74 L in the left tank and 130 L in the right. In the afternoon, the pilot prepared for the return flight to Stawell but inadvertently omitted to select the right tank and, at 1429, the aircraft departed Horsham with the left tank still selected.
The pilot reported that their practice was to use the crossing of en route waypoints as a cue to check the fuel state of the aircraft, but for the short flight to Stawell, the aircraft did not cross any en route waypoints and, at 1446, landed with the left tank still selected. At 1534, the aircraft departed Stawell with the left tank still selected and tracked toward the first en route waypoint, ESDIG. However, prior to crossing ESDIG, air traffic control instructed the pilot to track direct to waypoint IGNES.
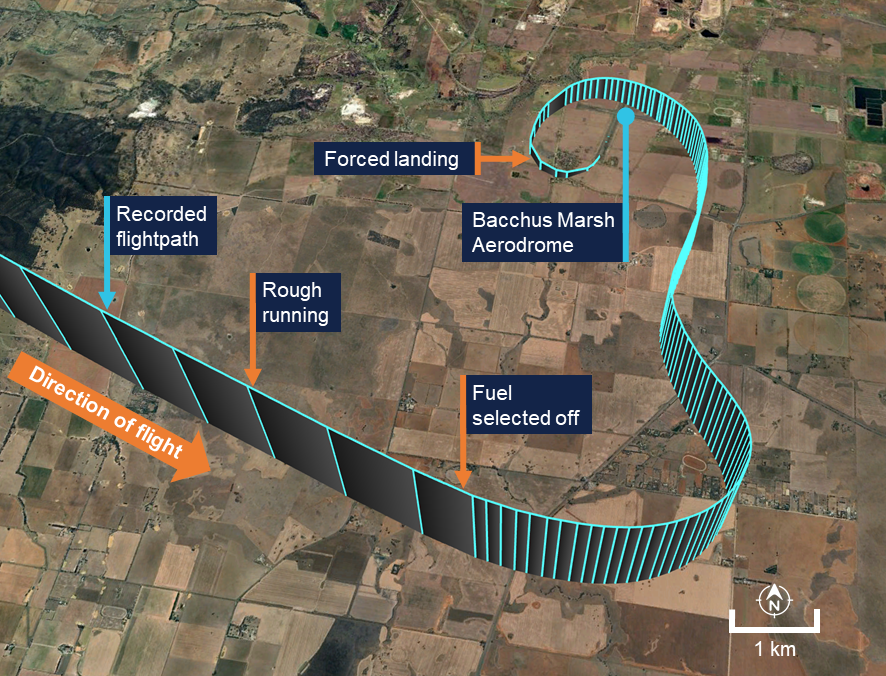
At 1616, the aircraft was continuing toward IGNES at 7,000 ft above mean sea level and passed through a patch of cloud. At that time, the engine began to run rough. Before commencing emergency procedures (see the section titled Emergency procedures) the pilot visually identified Bacchus Marsh Aerodrome, which was about 4 NM (7.4 km) north of the aircraft, as a suitable location for a forced landing (Figure 2). The engine continued to run rough and, in response, the pilot commenced the engine power loss in flight actions and selected the right fuel tank.
After switching fuel tanks, normal engine power did not immediately return, and the pilot assessed that the rough running was not fuel‑related. The pilot then shut the engine down by moving the mixture control to the idle cut-off position and the fuel selector to the off position.
Figure 2: Rough running and forced landing
Source: Google Earth and Airservices Australia, annotated by the ATSB
The pilot then completed a power-off landing at Bacchus Marsh without incident. After landing, the engine was started with the right fuel tank selected and ran without issue.
Context
Pilot details
The pilot held a Commercial Pilot Licence (Aeroplane), an instrument rating and a class 1 aviation medical certificate. The pilot had about 1,360 hours of aeronautical experience (105 in the Saratoga) of which 54 hours (29 in the Saratoga) were in the 90 days before the incident.
The ATSB found no indicators that the pilot was experiencing a level of fatigue known to adversely affect performance.
Aircraft details
General
The Piper PA-32R-301 Saratoga is a single-engine, low-wing, retractable-tricycle landing gear aircraft. The Saratoga is powered by a Lycoming IO‑540 fuel‑injected, horizontally‑opposed piston engine driving a 3‑blade, variable‑pitch propeller. VH‑LPW (Figure 3), serial number 32R‑8113095, was manufactured in the United States in 1981 and first registered in Australia in 1982.
Figure 3: VH-LPW
Source: Dallas Presser, modified by the ATSB
Fuel information
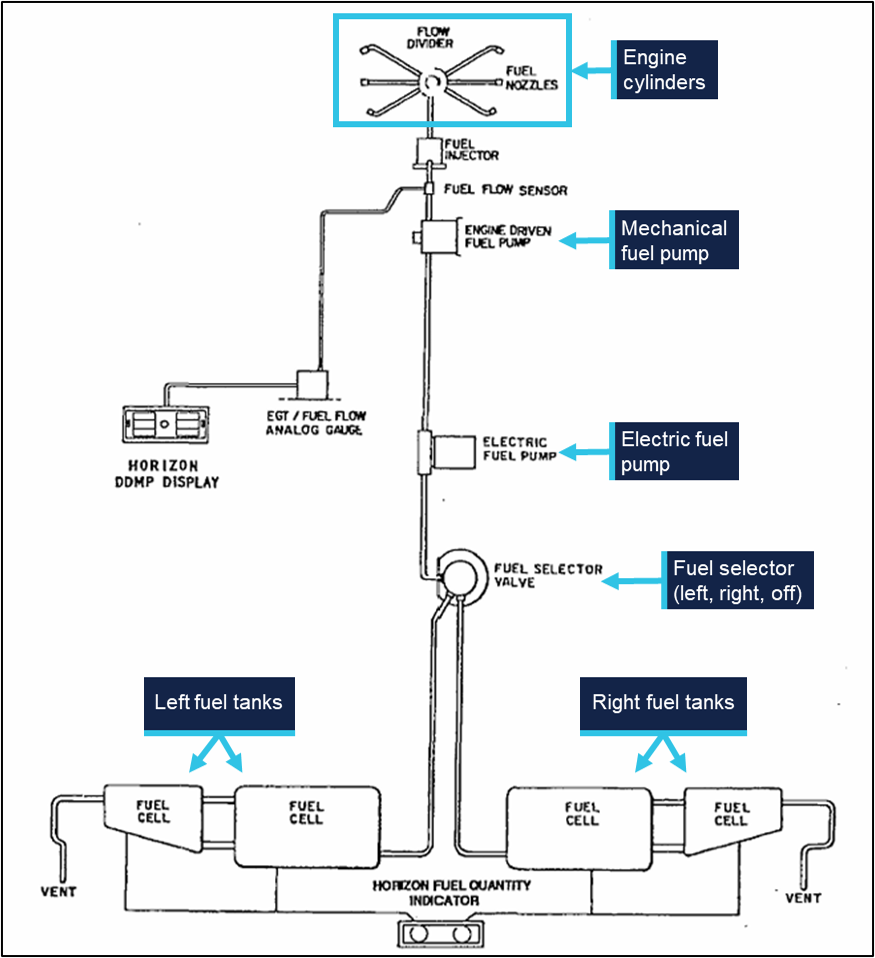
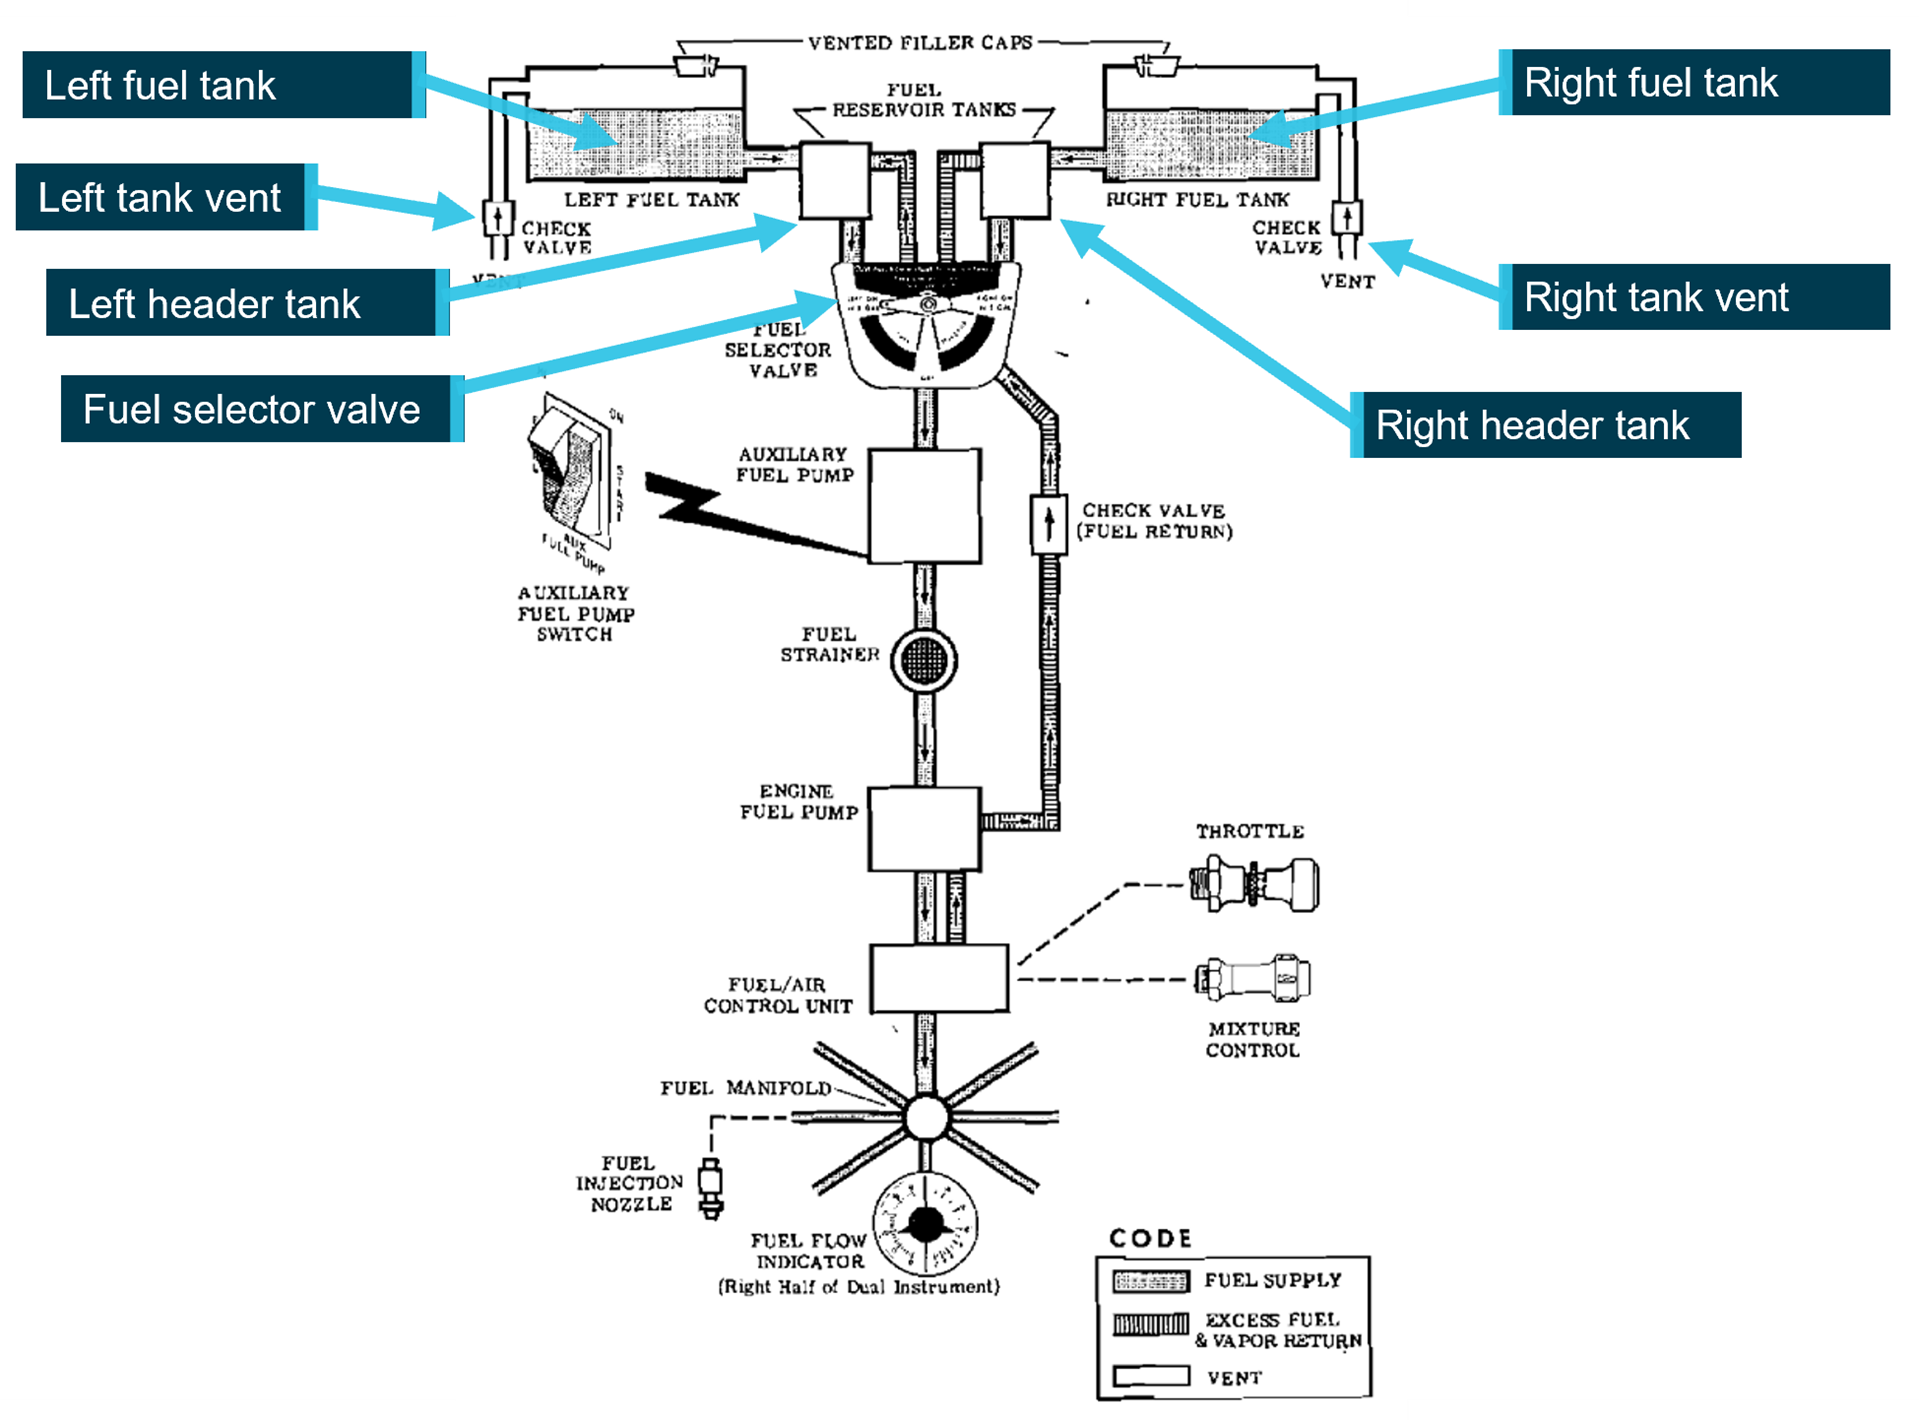
The Saratoga was fitted with 2 fuel tanks in each wing. The total fuel capacity was 405 L, of which 386 L was usable (193 L in each wing). The 2 fuel tanks in each wing were interconnected and acted as one tank and the fuel selector had 3 positions: left, right and off. Fuel was fed to the engine cylinders via a mechanical fuel pump and a pilot‑selectable electric fuel pump (Figure 4).
Figure 4: Fuel system schematic
Source: Piper, annotated by the ATSB
For normal operations, the pilot’s operating handbook (POH) required the following fuel tank selections when operating the aircraft:
• Before starting engine – Select desired tank
• Before take-off – Select the proper (fullest) tank
• For approach and landing – Select the proper (fullest) tank
For flight planning purposes, the pilot used an estimated en route fuel burn rate of 60 L per hour (consistent with POH information) and an allowance of 5 L for ground operations. The ATSB calculated that the aircraft departed Stawell for the return flight to Essendon with about 45 L in the selected left tank and 130 L in the right tank.
Emergency procedures
The POH instructed the following actions to be taken in response to an engine power loss in flight:
• Fuel selector – switch to tank containing fuel
• Electric fuel pump – select on
• Mixture rich – rich
• Alternate air – open
• Engine gauges – check for indication of cause of power loss
If no fuel flow is indicated, check tank selector position to be sure it is on a tank containing fuel.
The POH also noted that if the engine failure was caused by fuel starvation, engine power would not be restored after switching fuel tanks until the empty fuel lines were filled. The handbook stated that this could take up to 10 seconds.
Operation
The aircraft operator was an allied health services provider that serviced regional areas. The operator used small aircraft (and other means) to transport employees from major centres to the regional areas for appointments.
The operator’s flights were conducted in accordance with Civil Aviation Safety Regulation (CASR) instrument EX68/24 (section 7AA). This instrument provided an exemption to the requirements of CASR Part 119 (Australian air transport operations), permitting the flights to be operated under CASR Part 91 (General operating and flight rules) as private flights.
In addition to the exemption, the Civil Aviation Safety Authority (CASA) had also issued a direction applicable to flights conducted by the operator with the following additional requirements:
• In addition to meeting other CASR Part 61 (Flight crew licencing) requirements for the aircraft and the flight, each flight must be operated by a pilot in command holding a:
- Class 1 or Class 2 medical certificate
- Commercial Pilot Licence or Air Transport Pilot Licence.
• The aircraft must be operated in accordance with the performance rules specified in CASR Subpart 135.F, as if the flight were conducted as a Part 135 (air transport – smaller aeroplanes) operation.
• The aircraft must be compliant with the equipment rules in CASR Subpart 135.K, as if the flight were a Part 135 operation.
• Any aircraft used must be within the maximum take-off weight limits and maximum operational passenger seating capacity limits specified in regulation 135.005 of the CASR.
• The operator must ensure that all passengers carried are informed that the flight is being conducted as a private flight and that the flight is therefore not subject to all of the same safety standards as a commercial operation.
Meteorological information
At the time the engine began running rough, the aircraft was flying through broken2 clouds, although the forced landing was conducted in visual meteorological conditions.3
At 1600, 16 minutes before the incident, the Bureau of Meteorology automatic weather station at Avalon Airport, 26 km south of the aircraft, recorded the temperature as 27°C and the wind as 12 kt from 358° magnetic. Broken cloud was recorded at 8,935 ft above mean seal level, and visibility was recorded as greater than 10 km.
Similar occurrences
The ATSB has investigated multiple fuel management/fuel starvation incidents and accidents involving both single and twin‑engine aircraft. Examples include:
Fuel starvation event involving Cessna 310, VH-JQK, near Sunshine Coast Airport, Queensland, on 18 August 2022 (AO‑2022‑040).
Fuel starvation and forced landing involving Pilatus Britten-Norman Islander BN2A, VH‑WQA, Moa Island, Queensland, on 3 October 2022 (AO‑2022‑046)
Fuel starvation and forced landing involving Piper PA-31-350, VH-HJE, 11 km south of Archerfield Airport, Queensland, on 7 April 2023 (AO‑2023‑017).
Fuel starvation and ditching involving Piper PA-28, VH-FEY, 15 km north-west of Jandakot Airport, Western Australia, on 20 April 2023 (AO‑2023‑021).
Fuel starvation and forced landing involving Cessna 310R, VH-DAW, about 5 km south-east of Derby Airport, Western Australia, on 20 June 2023 (AO‑2023‑029).
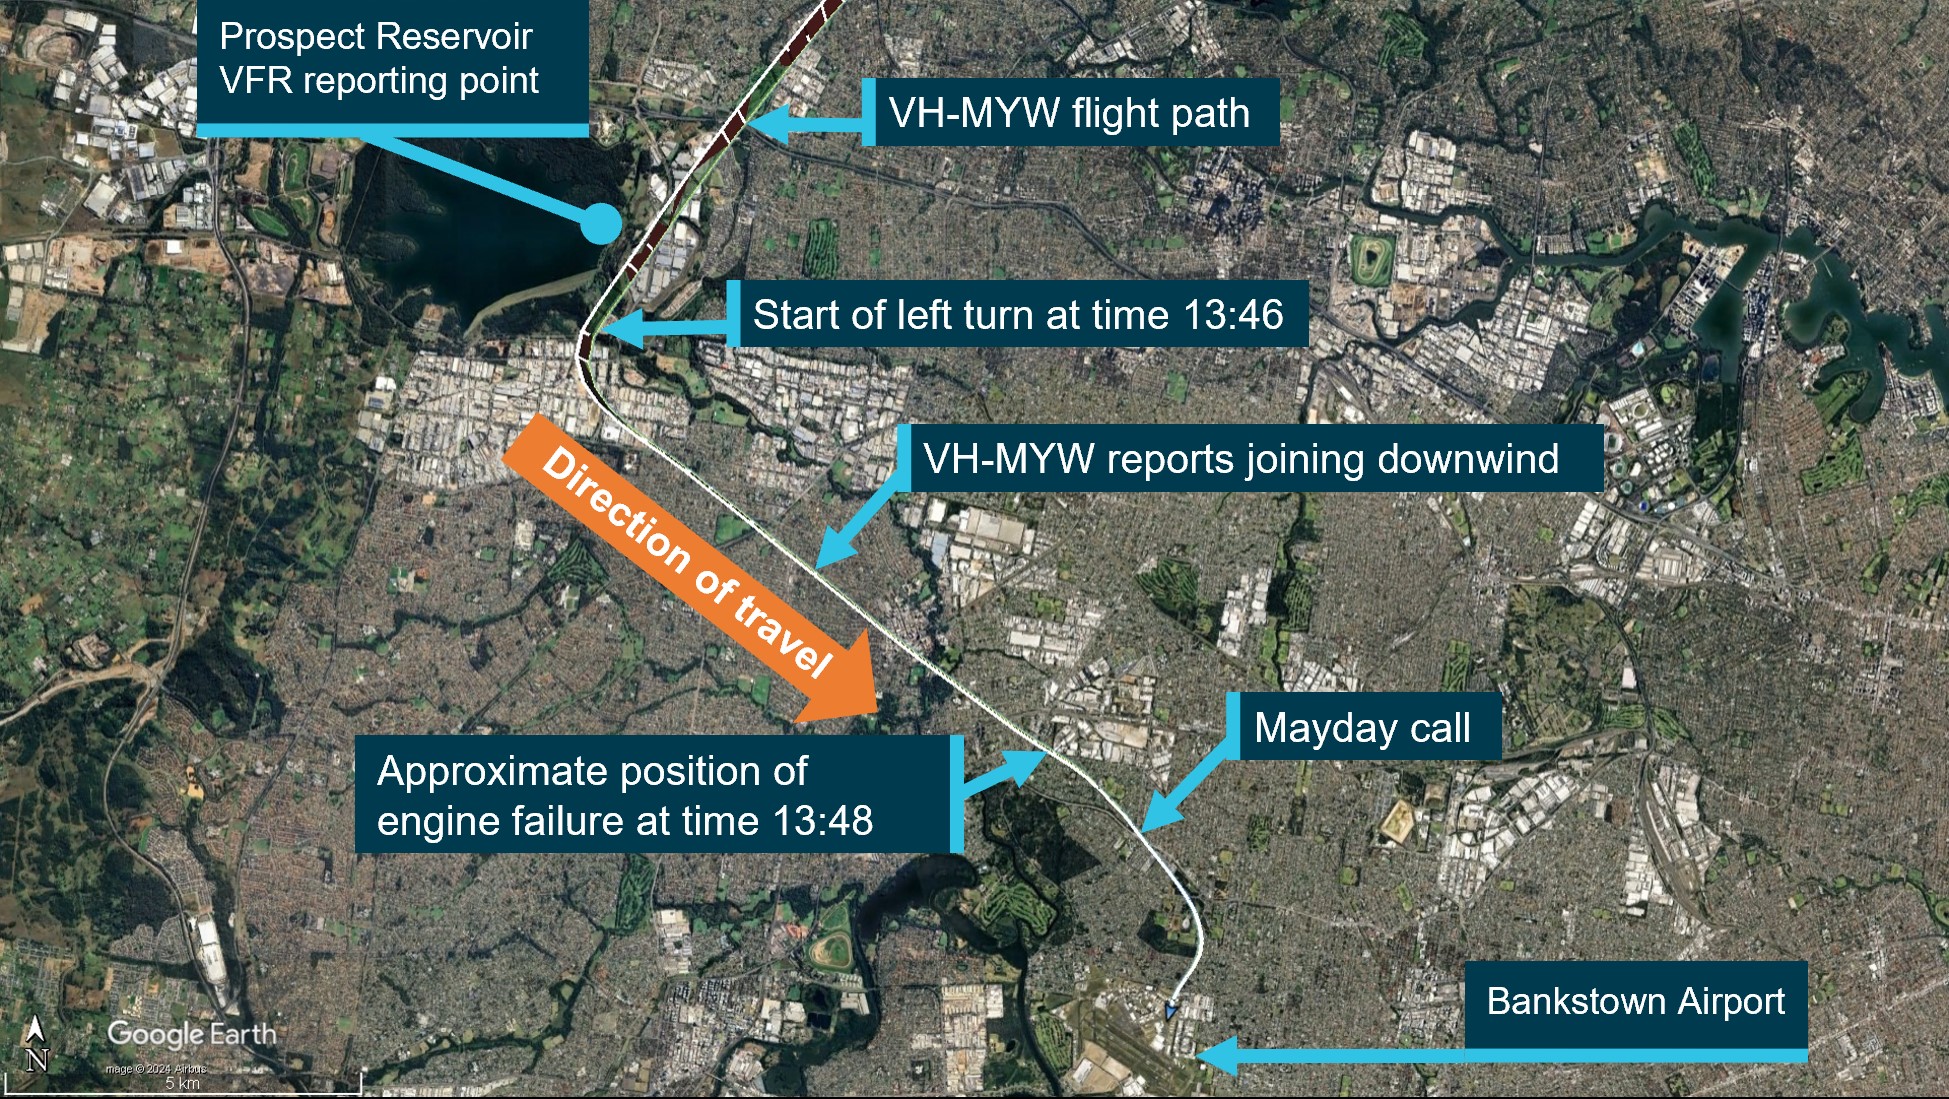
Fuel starvation involving Cessna T210M, VH-MYW, 4 km north‑west of Bankstown Airport, New South Wales, on 26 May 2024 (AO‑2024‑033).
Fuel starvation involving Cessna T210M, VH-LLM, near Darwin Airport, Northern Territory, on 8 September 2025 (AO‑2025‑054).
Safety analysis
The aircraft departed Moorabbin with sufficient fuel to conduct the day’s planned flying and the pilot planned to operate the legs to Horsham on the left tank and return on the right. While this plan provided adequate fuel supply to the engine for the day, it was not consistent with the pilot operating handbook’s (POH) requirement to select the fullest tank for the arrival into Horsham (when fuel level in the left tank had reduced below that of the right tank).
At Horsham, the pilot inadvertently omitted the planned selection of the right tank for the return flights and then, prior to departure, the fullest (right) tank was not identified and selected as required by the POH. During the return flight to Stawell, the aircraft did not cross an en route waypoint. As a result, the pilot was not prompted by their usual processes to review the aircraft’s fuel state and identify the omission.
The pilot’s plan for the day’s flying did not include further tank selections and therefore the pilot was likely not primed to make any further selections. Nevertheless, for the landing and departure from Stawell, the pilot did not select the fullest (right) tank as was required, nor did they identify that the left tank remained selected. Therefore, the aircraft departed Stawell with about 45 L available in the selected tank. This was insufficient fuel to complete the flight.
After the departure from Stawell, air traffic control instructions resulted in a change to en route tracking prior to the aircraft crossing the waypoint ESDIG. As the pilot’s practice of reviewing the fuel state was linked to crossing waypoints, the change in tracking resulted in the pilot not being prompted to identify the fuel tank selection omission before the fuel in the left tank was exhausted. As a result, at 1616, the contents of the left tank were exhausted, and the engine began to run rough.
Contributing factor
On a previous flight leg, a planned fuel tank change was inadvertently omitted. The omission was not detected prior to the contents of the left fuel tank being exhausted and the engine began running rough.
In response to the rough running, the pilot commenced the emergency actions and changed to the right fuel tank. After taking this action, the POH instructed that it could take up to 10 seconds for the empty fuel lines to be filled before the engine would restart. However, the pilot almost certainly did not allow this time to elapse before assessing that the engine failure was not fuel‑related and shutting off fuel to the engine.
After shutting off the fuel, the pilot then successfully completed a forced landing at Bacchus Marsh. After landing, the serviceability of the engine was confirmed when a start was attempted and, after sufficient time was allowed for the empty fuel lines to be filled, the engine started and ran without issue.
Shutting off the fuel to the engine before sufficient time had elapsed for it to restart resulted in an unnecessary forced landing that increased risk to the flight.
Contributing factor
In response to the rough running, the appropriate emergency actions were not fully completed, and the engine was shut down before those actions could take effect. A landing was then completed without engine power.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the fuel starvation involving Piper PA-32R-301, VH-LPW, 9 km south of Bacchus Marsh Aerodrome, Victoria, on 1 May 2026.
Contributing factors
On a previous flight leg, a planned fuel tank change was inadvertently omitted. The omission was not detected prior to the contents of the left fuel tank being exhausted and the engine began running rough.
In response to the rough running, the appropriate emergency actions were not fully completed, and the engine was shut down before those actions could take effect. A landing was then completed without engine power.
Sources and submissions
Sources of information
The sources of information during the investigation included:
Airservices Australia
Civil Aviation Safety Authority
Piper Aircraft
the Bureau of Meteorology
the operator
the pilot.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
Civil Aviation Safety Authority
Piper Aircraft
the operator
the pilot
United States National Transportation Safety Board.
Submissions were received from:
Civil Aviation Safety Authority
the operator.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of an ATSB safety investigation is to improve transport safety through:
identifying safety issues for action by organisations with the responsibility for managing that safety risk
influencing safety action through engaging with stakeholders, communicating findings, and fostering awareness of safety issues and concerns.
In accordance with the TSI Act, the ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action, and cannot apportion blame, assist in determining liability, or, as a general rule, assist in court proceedings.
About ATSB reports
ATSB safety investigation reports are developed in accordance with ATSB procedures and guidelines, and with regard to applicable international standards and instruments.
Reports must include factual material of sufficient weight to support the investigation’s analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.
An explanation of terminology used in ATSB investigation reports is available here.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau.
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
^Instrument flight rules (IFR): a set of regulations that permit the pilot to operate an aircraft in instrument meteorological conditions (IMC), which have much lower weather minimums than visual flight rules (VFR).
^In aviation, cloud cover is reported using words that denote the extent of the cover – ‘broken’ indicates that more than half to almost all the sky is covered.
^Visual meteorological conditions (VMC): an aviation flight category in which visual flight rules (VFR) flight is permitted – that is, conditions in which pilots have sufficient visibility to fly the aircraft while maintaining visual separation from terrain and other aircraft.
The ATSB is investigating a fuel starvation event involving a Piper PA-32, VH-JFC, near Rottnest Island Airport, Western Australia, on 1 May 2026.
Shortly after take-off, at an altitude of about 1,000 ft, the pilot detected a partial power loss and elected to return to Rottnest Island Airport. The pilot reported initiating troubleshooting checks, which included activating the fuel pump and selecting the right fuel tank. Engine power was restored and the pilot proceeded to land on runway 27 at Rottnest Island Airport.
The evidence collection phase of the investigation will involve:
interviewing involved parties
retrieving and reviewing recorded data
collection of other relevant information.
A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.
Occurrence summary
Investigation number
AO-2026-075
Occurrence date
01/05/2026
Occurrence time and timezone
16:30 Australian Western Standard Time
Location
Near Rottnest Island
State
Western Australia
Report status
Pending
Anticipated completion
Q4 2026
Investigation level
Short
Investigation type
Occurrence Investigation
Investigation phase
Evidence collection
Investigation status
Active
Mode of transport
Aviation
Aviation occurrence category
Diversion/return, Engine failure or malfunction, Fuel starvation
Occurrence class
Serious Incident
Highest injury level
None
Aircraft details
Manufacturer
Piper Aircraft Corp
Model
PA-32-260
Registration
VH-JFC
Serial number
32-7100025
Aircraft operator
Wadjemup Aerial Service Pty Ltd
Sector
Piston
Operation type
Part 135 Air transport operations - smaller aeroplanes
Activity
Commercial air transport-Non-scheduled-Passenger transport charters
On the evening of 8 September 2025, a Cessna T210M, registered VH-LLM, was conducting night take-offs and landings at Darwin Airport, Northern Territory. On board was an instructor from a training organisation and a student who was doing their first night training flight and owned the aircraft. After completing several take-offs and landings, the instructor directed the student to conduct a go-around. Shortly after turning downwind, the aircraft lost power. The student handed control of the aircraft to the instructor and made a MAYDAY call.
The instructor initiated troubleshooting checks and determined that the fuel selector was set on the right tank and was likely empty. The instructor activated the electric fuel pump before selecting the left tank which restored engine power and the aircraft was recovered into a climb. The student resumed control and proceeded to land safely at Darwin Airport.
What the ATSB found
Fuel was not selected to the fullest tank during multiple circuits resulting in a loss of power.
The student did not effectively conduct the pre-landing checks to monitor the fuel state of the aircraft. This was likely due to an increased workload during their first night flight in controlled airspace. In addition, the configuration of the primary flight display was changed to show airport maps, resulting in a smaller fuel gauges display in a different location, unfamiliar to the student.
The instructor had identified that the student had not changed tanks during previous circuits (a requirement to land on the fullest tank) and had intended to discuss this. However, the instructor later became focused on monitoring the student’s performance and forgot to brief the student on changing to the fuller tank.
In addition, before the flights, the student did not visually inspect the quantity of fuel on board the aircraft prior to departure and relied on the instructor’s recollection the aircraft had adequate fuel for the training session.
Safety message
Fuel starvation occurrences can often be prevented by conducting thorough pre-flight fuel quantity checks combined with in‑flight fuel management.
Although pre-landing checks are routine, they must never become perfunctory. Pilots must understand the purpose behind each check, ensuring the aircraft is properly configured for landing according to the aircraft guidance.
Pilots are reminded to independently visually check fuel quantities prior to departure and use a known calibrated instrument such as a dipstick in addition to fuel gauge readings.
Pilots should familiarise themselves with the Civil Aviation Safety Authority, Advisory Circular AC 91-15v1.1 Guidelines for aircraft fuel requirements, which provides further guidance for in‑flight fuel management.
The investigation
The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On the evening of 8 September 2025, a Cessna T210M, registered VH-LLM, was being used to conduct night visual flight rules (NVFR) training circuits[1] at Darwin Airport, Northern Territory. The student was a licensed pilot who owned VH-LLM, and also on board was an instructor from the training organisation, Flight Standards.
The day before the flight, the student refuelled the aircraft to capacity and flew it from Emkaytee aerodrome, Northern Territory, to Darwin Airport. On the morning of the training session, the instructor, who had not previously flown a turbo Cessna 210, took the aircraft for a familiarisation flight, accompanied by Flight Standards’ chief flying instructor. The student reported that they had given permission for the flight but were unaware of the route taken or the amount of fuel used.
The instructor recalled dipping the fuel tanks after completing the familiarisation flight that morning, recording a total of about 55 L in the left tank and 75 L in the right tank. The instructor assessed that the total remaining fuel quantity was sufficient for the planned night circuit training session.
The student arrived at the airport at about 1800 local time[2] and conducted a pre-flight check with the instructor. The student asked whether there was sufficient fuel in the aircraft for the flight and received confirmation from the instructor that there was sufficient fuel. Subsequently, no visual inspection of the aircraft fuel quantity was carried out by the student.
For the flight, the student occupied the left seat with the primary flight display (PFD) directly in front of them and the instructor sat on the right. The student reported noticing that the instructor had altered the configuration of the PFD from their normal set up of engine instruments, to a split screen with a map of Darwin Airport taxiways on the right of the screen.
As this was the student’s first night flight the instructor reported spending additional time briefing the student on night circuits after engine start, which included aircraft lighting and other general information for night flying, before the student conducted engine run-ups at about 1914. During this time, the fuel selector was positioned on the left tank.
The aircraft pilot operating handbook (POH)[3], as well as the training organisation’s flight crew operating manual (FCOM), stated that it was a requirement to take off and land on the fullest tank. The student reported that at the beginning of the flight, this was the right tank. Before handing control to the instructor to demonstrate the first circuit, the student switched from the left to the right tank.
After completing the demonstration, while on the runway, the instructor briefed the student on the focus of the next circuit before the student took control from the left seat.
At about 1952, on completion of the student’s first landing, the instructor noticed that the student had conducted the pre-landing fuel check using a non-standard mnemonic checklist and identified that the student did not turn on the landing lights and that the flaps were not at the correct position. The student did not change the fuel selector from the right tank. As the instructor believed there was more fuel in the right tank at that time, they were comfortable with the student’s actions and did not direct them to change tanks before continuing with the next circuit. The instructor reported they debriefed the student on checklist discipline.
The fuel selector was not changed on the student’s second or third circuit. The instructor noted that the student’s use of a mnemonic checklist was not completely effective in ensuring that the actions in the checklist were completed for landing. In particular, this included that the student’s checklist did not cover the challenge/response to the fuel check as per the POH to ensure that the fuel selector was set to the fullest tank. The student reported their increased concentration on flying the aircraft at night detracted from monitoring the fuel gauge in the altered position. The instructor reported they had planned to request the tanks be changed on the next downwind leg.
At about 2030, during the student’s fourth circuit, the instructor directed the student to conduct a go-around[4] while on the final approach due to an aircraft behind them. The instructor recalled that the go-around was not completed proficiently and mentally noted to brief the student at the next opportunity to change the fuel selector to the left tank.
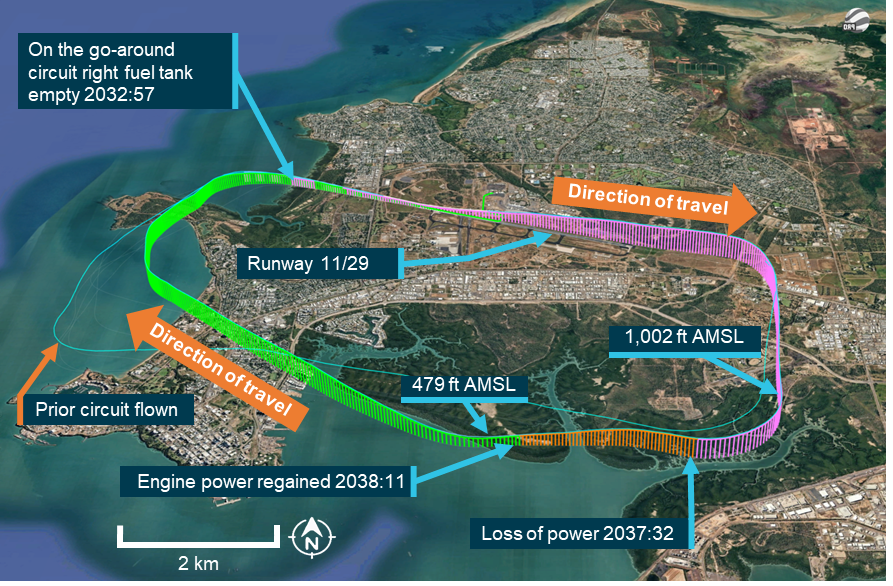
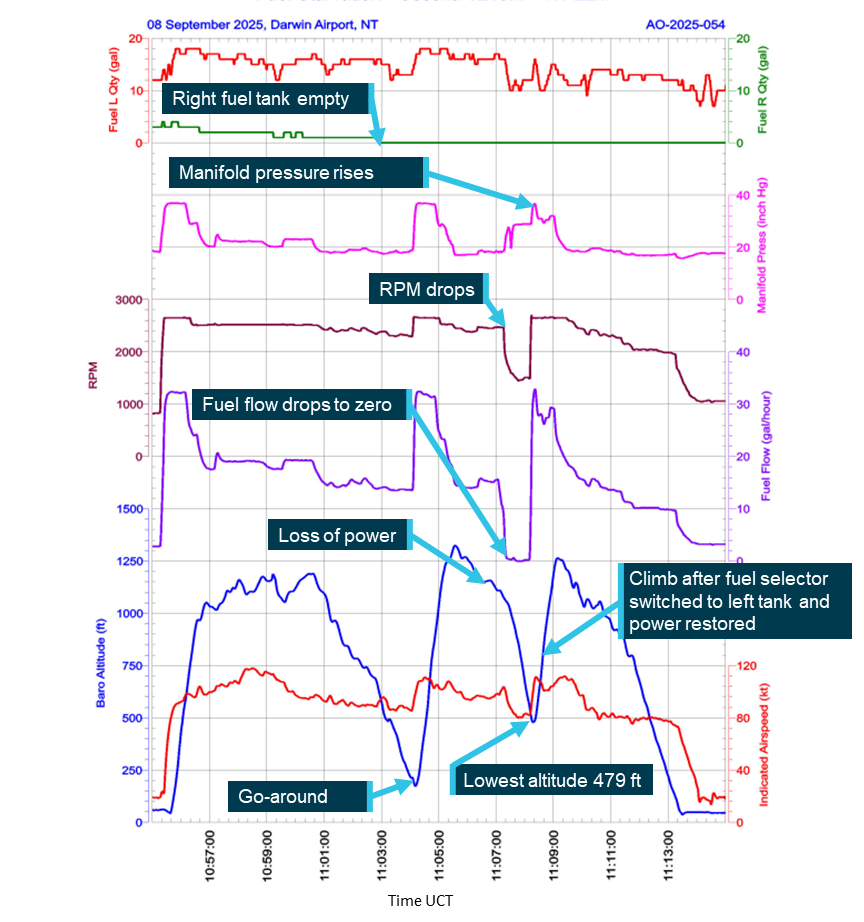
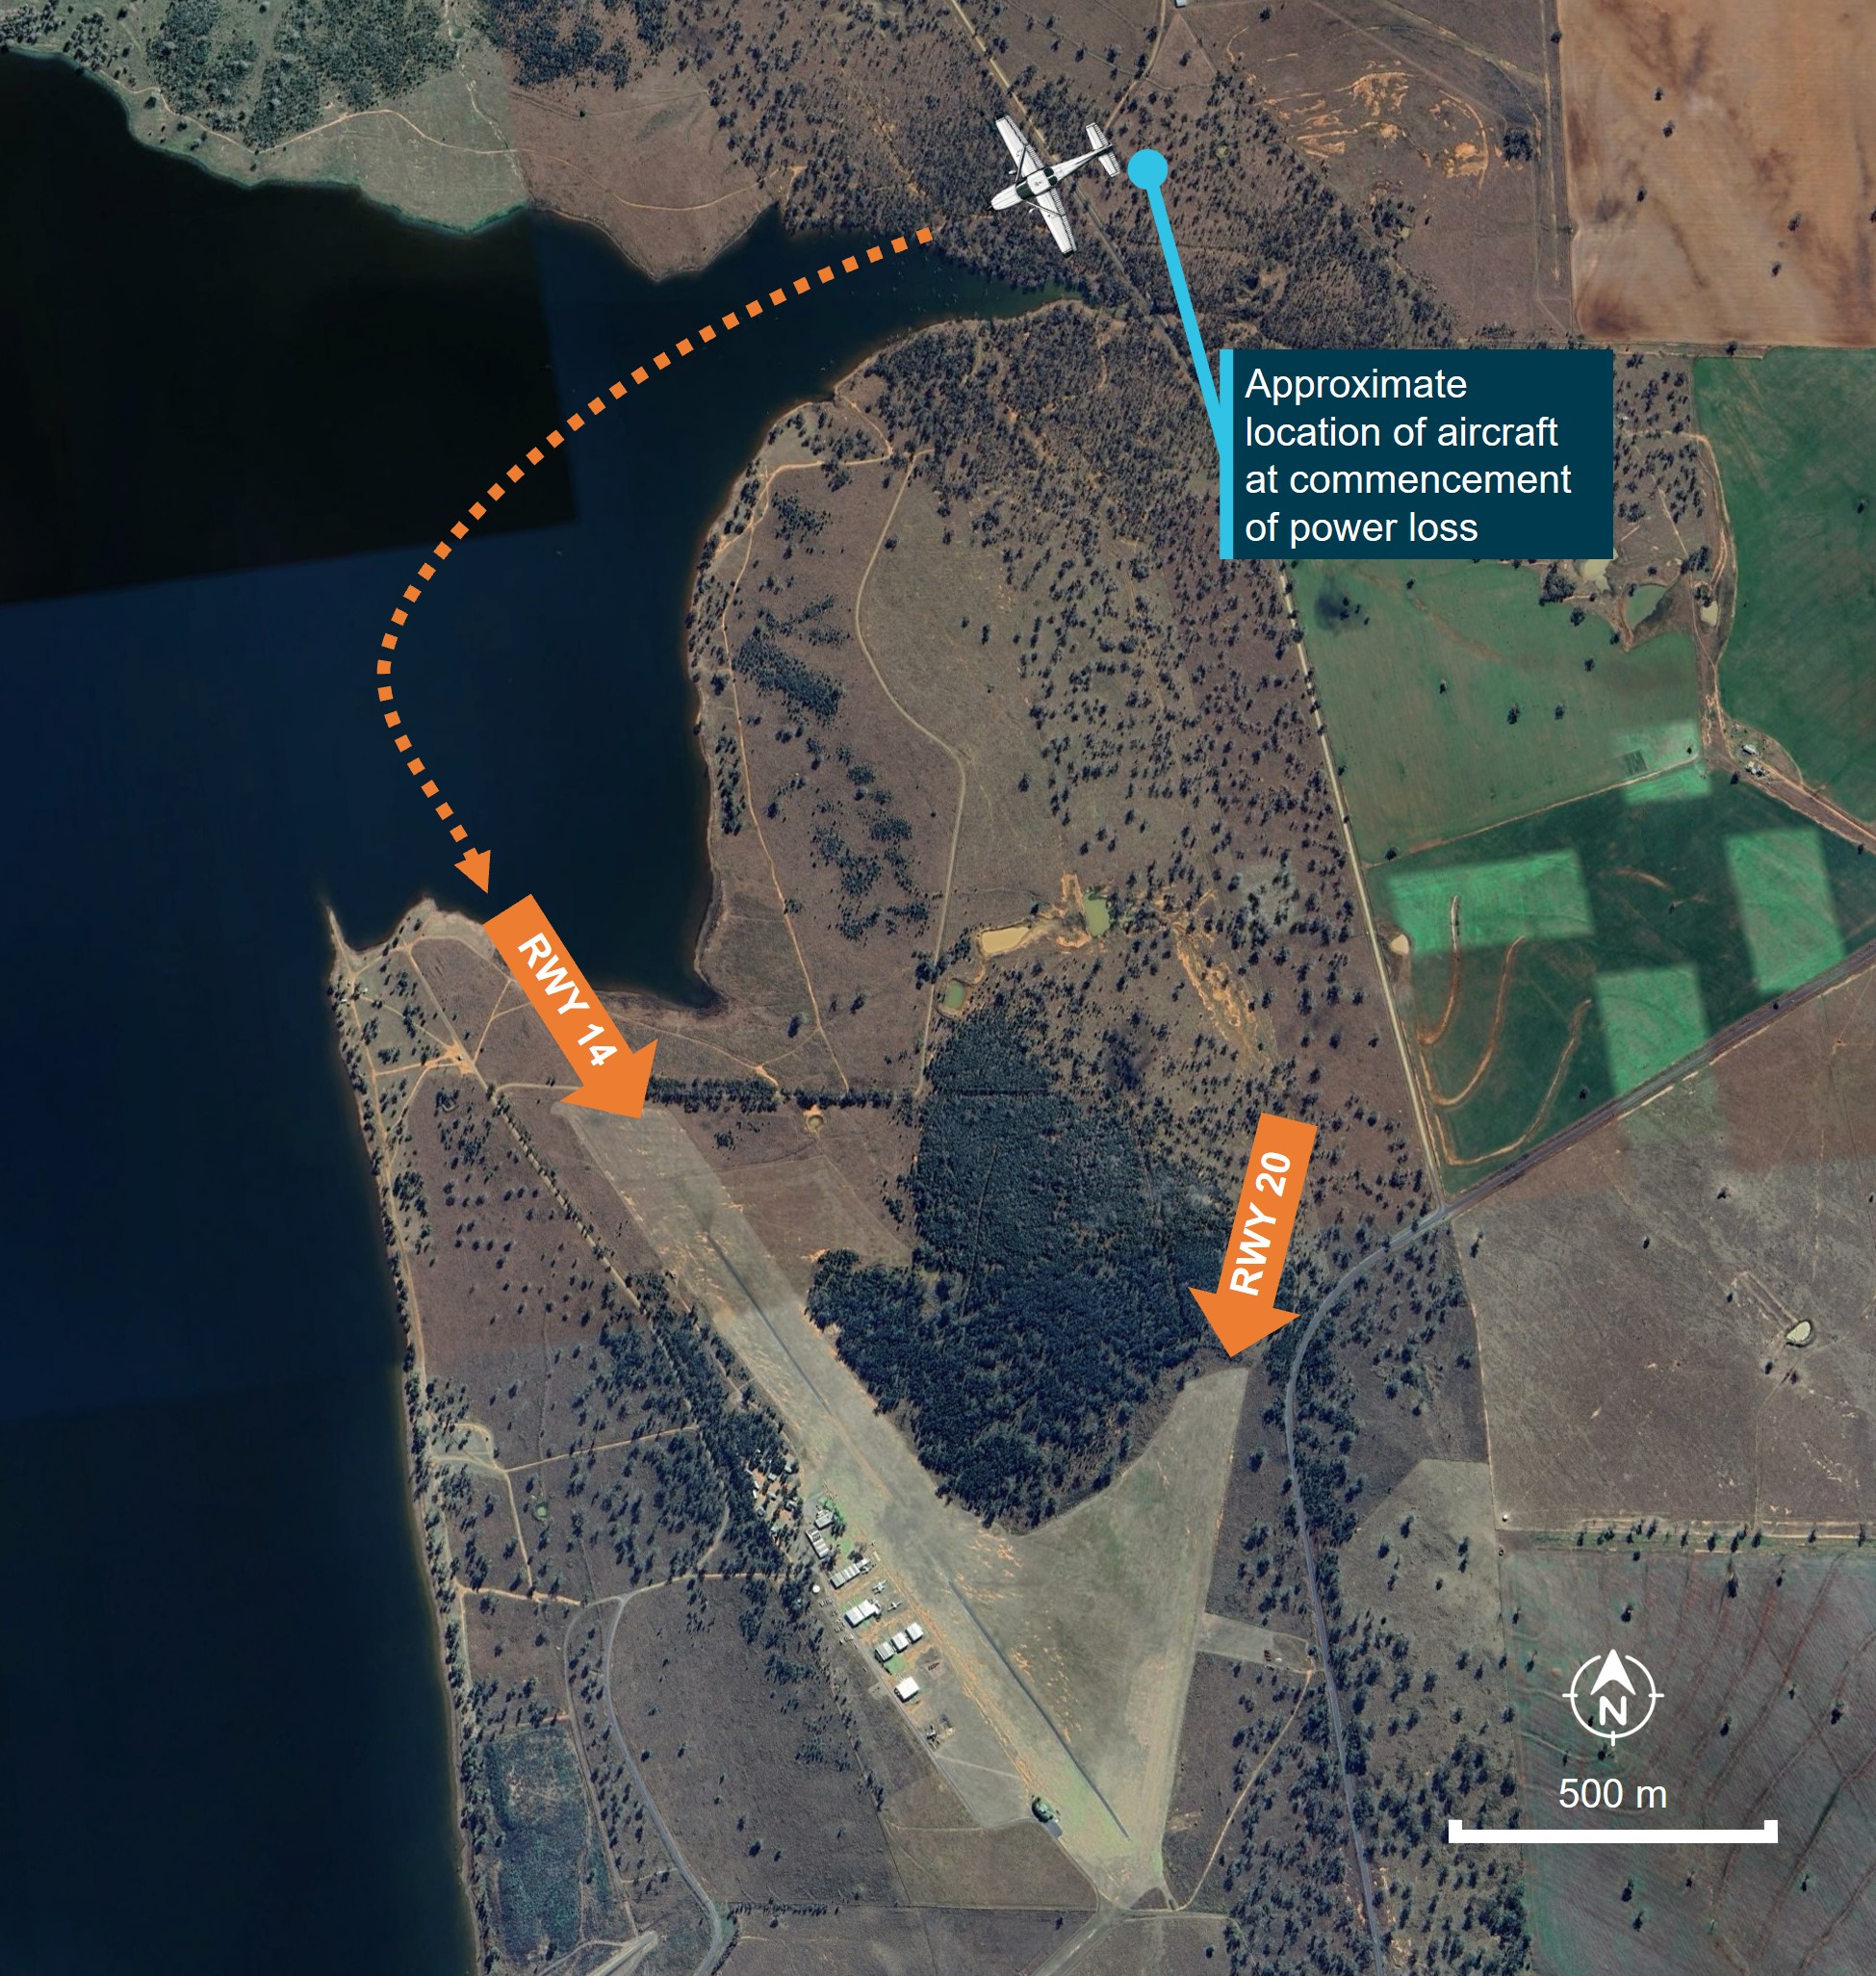
At 2032:57, recorded data showed that the right fuel tank indicated zero fuel before conducting the go-around, but the aircraft engine continued running using fuel in the lines and header tank (Figure 1).
At 2037:32, after turning onto the downwind circuit leg, the engine began to lose power and, realising that a return to the airport was not achievable, the student handed control to the instructor. The instructor conducted troubleshooting while the student declared an emergency to air traffic control (ATC).
The instructor identified that the aircraft fuel selector was positioned on the right fuel tank and realised that the tank, which had not been changed since beginning the circuits, was likely empty. They followed the POH procedure to change tanks, activated the auxiliary fuel pump and changed the fuel selector to the left tank. This restored engine power and they initiated a climb. The aircraft was at 600 ft above ground level at this time, and the crew heard an alert from ATC. The student responded and cancelled the emergency with the tower.
Once established in the climb, the student assumed control, recovered the aircraft back into the circuit and landed safely at Darwin Airport without further incident.
Post-flight inspection by maintenance personnel reported no mechanical defects with the aircraft fuel system or engine.
Figure 1: Graphical depiction of the occurrence circuit
Source: Google Earth, annotated by the ATSB
Context
Pilot information
Instructor
The instructor attained their Commercial Pilot Licence (Aeroplane) in 2021 with class ratings for single and multi-engine aircraft. They completed their Grade 2 instructor qualifications in December 2024. They held an NVFR endorsement and had a total of about 1,270 flying hours, of which about 800 hours were instructional. The instructor reported that at the time of the occurrence they had accrued 27.6 hours of night flight experience. Their most recent night flying activity prior to the occurrence was a flight instructor rating flight test conducted on 28 July 2025. The instructor was subsequently approved by the operator to carry out instructional flights at night, and the occurrence flight was the first instance of this.
The instructor had about 70 hours experience in non‑turbocharged models of Cessna 210 aircraft. The instructor held a current Class 1 medical certificate.
They reported sleeping for 8 hours the night before the occurrence and identified that they had slept for about 4 hours that afternoon. They reported their level of alertness as a ‘3‑ Okay somewhat fresh’ on a scale of 1–7 where, 1 is fully alert and 7 is completely exhausted.
Student
The student held a Private Pilot Licence (PPL) for a single‑engine aeroplane issued in 2018, held a current Class 1 medical certificate and had a total experience of about 412 hours of which 123.5 hours were completed in VH-LLM. They had completed 2 NVFR training sessions in the Flight Standards’ simulator prior to the occurrence. The student had flown day VFR for several years and wished to obtain a NVFR endorsement along with practice in procedures for Class C controlled airspace.
The student reported having a normal amount of sleep the night before and following their usual routine of breakfast and a light lunch. They worked a busy but uneventful day from about 0800 before arriving at the airport for the lesson at 1800. The student indicated they were fully alert on a scale of 1–7, where 1 is fully alert and 7 is completely exhausted.
Aircraft information
The aircraft was a Cessna Aircraft Company T210M, 6‑seat, high-wing aircraft manufactured in 1977. It was powered by a Teledyne Continental Motors Inc TSIO-520 turbocharged, fuel‑injected piston engine driving a 3-bladed, constant-speed McCauley propeller. The cockpit consisted of side-by-side seating for the pilot/student on the left and instructor/passenger on the right. The aircraft was initially registered on 6 June 1989 and then transferred to the current owner on 27 March 2023.
Glass cockpit
The cockpit of VH-LLM had been retrofitted with a customisable Garmin G3X suite (GI 275) glass cockpit.[5] The student reported that on the night of the training session the instructor had changed the screen from the configuration that the student was previously used to. This included a change to the location of the fuel gauge which was positioned at the far left of the screen rather than on the right (Figure 2).
Figure 2: Photograph of VH-LLM Garmin G3X screen configuration changes
Source: Aircraft owner, annotated by the ATSB
The instructor reported that there were no audio or visual fuel‑related alerts associated with low fuel quantities or reminders to switch the fuel tank selection in the display. The instructor reported that the location of the fuel gauge was difficult to see from their seat position on the right-side of the aircraft.
Both the student and instructor reported that the fuel gauge was less visually prominent in the new screen configuration and more difficult to monitor.
Fuel
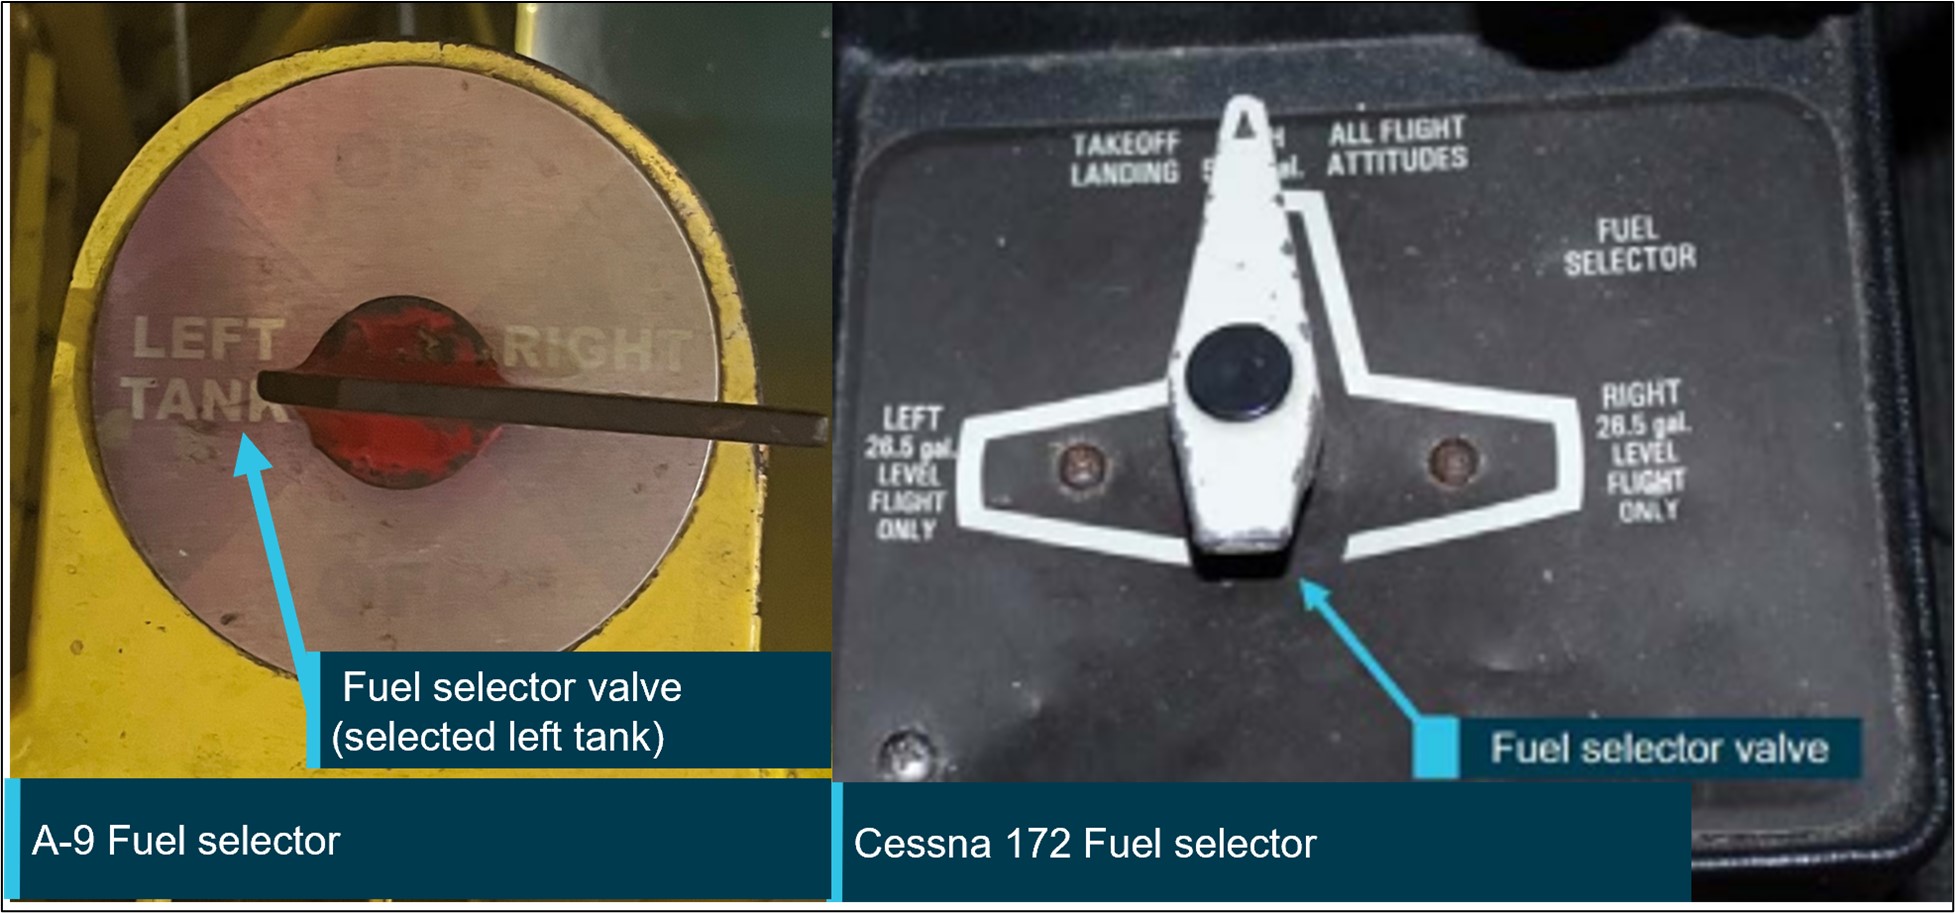
The Cessna 210 fuel system consists of 2 main fuel tanks, 1 in each wing. Each tank has a capacity of 171 L, of which 169 L is usable. The fuel selector valve had 3 positions – left, right and off. Fuel could only be drawn from either the left or right tank during normal operations. The fuel system has an engine-driven fuel pump and an electrically‑driven auxiliary fuel pump. The pilot operating handbook (POH) stated:
If it is desired to completely exhaust a fuel tank quantity in flight, the auxiliary fuel pump will be needed to assist in restarting the engine when fuel exhaustion occurs.
The POH stated that a final 45 L reserve fuel should be available for operations. The chief pilot observed that 47 L remained in the left tank after landing.
Training organisation’s procedures for flight planning and fuel usage
The instructor reported that the training organisation’s fuel management guidance for circuit operations stated that circuit flights must plan to land with greater than final fuel reserve.[6]
The training organisation’s FCOM for the Cessna 210 (Section 2.5) stated that it was a requirement to take off and land on the fullest tank, with guidance in Section 7.1 stating:
For take-off and the first 30 minutes of flight, the fullest tank is selected and then tanks are cycled every 60 minutes thereafter, with the fullest tank selected for landing.
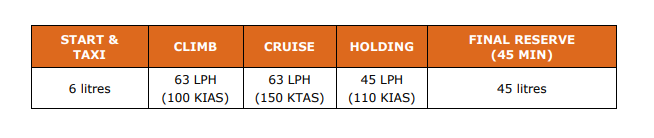
Section 5.3 provided typical fuel usage guidance in a table for fuel planning purposes (Figure 3).
Figure 3: Table provided for fuel management from the operator’s Cessna 210 FCOM
Source: Operator
The instructor commented that they were aware that the turbocharged 210 model had a slightly higher fuel burn, but they considered the amount of fuel available as adequate for the planned training session.
Meteorological information
The weather forecast for Darwin Airport indicated good flying conditions with no significant weather, no cloud below 5,000 ft, and visibility greater than 10 km. The automated observation at Darwin Airport for 2030 reported no cloud detected, visibility greater than 10 km, north‑easterly winds at 5 kt, temperature of 27°C and no rainfall.
Airport information
Darwin Airport is a joint civil and military facility. It services domestic and international air traffic and has 2 runways. The airport has an elevation of 103 ft above mean sea level (AMSL). The control tower provides a Class C controlled airspace around the airport, while outside of this area is class G uncontrolled airspace.
Recorded information
Flight data
The Garmin G3X avionics suite recorded to a secure digital (SD) card which was analysed by the ATSB (Figure 4).
Recorded data indicated that during the last circuit, the aircraft had descended from about 1,200 ft to 479 ft AMSL before then climbing.
Figure 4: Data obtained from the VH-LLM Garmin G3X SD card
Source: ATSB
Fuel data
The recorded fuel data identified that fuel from the right tank had been fully used at 2032:57, prior to commencement of the go-around. Due to the residual fuel in the system and header tanks, the engine power loss occurred about 5 minutes later at 2037:32. After conducting engine troubleshooting, the power was restored at 2038:11.
Fuel starvation
Fuel starvation refers to where the fuel supply to the engine is interrupted, although adequate fuel remains on board the aircraft. Fuel exhaustion refers to where the aircraft has depleted all useable fuel.
An ATSB study Avoidable Accidents No. 5 Starved and exhausted: Fuel management aviation accidents (AR-2011-112) regarding fuel starvation accidents found that in addition to accurate knowledge of fuel quantity at the start of a flight, the risks for fuel starvation are increased when pilots forget to change tanks during periods of low workload, or when pilots forget to select the appropriate tank prior to the approach to land. Although tank selection for approach and landing is often specified in the aircraft flight manual, following this procedure will only be successful if the pilot has also ensured that there is sufficient fuel in the required tank for landing.
Cognitive resources
Cognitive ability is a finite resource to pilots, and the limit of its availability plays a role in determining how effectively a pilot maintains adequate performance. Workload is a term used to describe the ‘cost’ for a human to fulfil certain task requirements. This cost can be reflected in the depletion of cognitive resources, the inability to conduct additional activities, emotional stress, fatigue or decreased performance (de Souza Borges and others, 2023). Workload and performance are intricately related as task demands are actively managed through resource allocation and strategy change (Loft and others, 2023).
An intention to perform a task at some future time is known as a prospective task. Prospective memory involves remembering, and sometimes forgetting, to perform tasks that must be deferred (Dismukes, 2010; Harrison and others, 2014).
In aviation, individuals typically must manage several concurrent tasks and consequently are often forced to postpone or interrupt tasks and attempt to remember to perform the deferred tasks later. A significant issue in prospective memory is not retention of the content of intentions, but retrieval of those intentions at the appropriate moment, which is often vulnerable to failure. Typically, if queried after forgetting to perform an action, an individual can recall what they intended to do.
Related occurrences
Fuel starvation occurrences highlight the critical importance of proper fuel management and pre‑flight planning. Fuel management and fuel starvation incidents and accidents have regularly occurred with single and twin-engine aircraft. Examples of other similar ATSB investigations include:
Fuel starvation and forced landing involving Piper PA-28, VH-BDB, 15 km west‑south‑west of Bankstown Airport, New South Wales, on 19 September 2017 (AO‑2017‑094).
Fuel starvation event involving Cessna 310, VH-JQK, near Sunshine Coast Airport, Queensland, on 18 August 2022 (AO-2022-040).
Fuel starvation and forced landing involving Pilatus Britten-Norman Islander BN2A, VH‑WQA, Moa Island, Queensland, on 3 October 2022 (AO-2022-046)
Fuel starvation and forced landing involving Piper PA-31-350, VH-HJE, 11 km south of Archerfield Airport, Queensland, on 7 April 2023 (AO-2023-017).
Fuel starvation and ditching involving Piper PA-28, VH-FEY, 15 km north-west of Jandakot Airport, Western Australia, on 20 April 2023 (AO-2023-021).
Fuel starvation and forced landing involving Cessna 310R, VH-DAW, about 5 km south-east of Derby Airport, Western Australia, on 20 June 2023 (AO-2023-029).
Fuel starvation involving Cessna T210M, VH-MYW, 4 km north-west of Bankstown Airport, New South Wales, on 26 May 2024 (AO-2024-033).
Safety analysis
The flight crew of VH-LLM experienced a loss of engine power during a night training flight. The instructor took command of the aircraft and quickly diagnosed that the fuel selector was on the right-wing tank and had not been changed for the duration of the circuits. The instructor activated the electric fuel pump and changed to the left tank which restored fuel and engine power to the aircraft.
This analysis will look at the use of appropriate checklists and the management of fuel prior to and during flight.
Fuel management
Student
The student did not visually verify the fuel quantity in the aircraft when conducting pre‑flight checks, instead they relied on the instructor’s confirmation that the aircraft had sufficient fuel on board but without informing the student how much fuel was in each of the tanks.
The student reported not monitoring the fuel gauge (which had been relocated on the primary flight display) due to the screen configuration change from the display that they normally used. Although the student used a mnemonic for pre-landing checks which included the fuel, the check was not completed with the required response that the fuel selector was set to the fullest tank in accordance with the pilot operating handbook.
In addition, the student reported the fuel gauge checks were a consequence of their need to concentrate on flying the aircraft in the night environment. Night flying increases cognitive and perceptual workload due to the decreased visual cues, the requirement for increased instrument monitoring and the risk of spatial disorientation (Biernacki and others, 2024). Further, this was the first time operating at night in controlled airspace for the student. The additional workload likely limited the student’s capacity for systematic visual scanning of cockpit instruments.
Instructor
The instructor reported noticing the student not switching tanks for the first circuit but was satisfied with the student’s decision as the tank in use was the fullest tank at that point. The instructor intended to monitor this on further landings and brief the requirement if it continued. However, during subsequent circuits, their focus shifted to monitoring the student’s performance and other demands such as other aircraft and the execution of the go-around.
As this was the instructor’s first instructional flight at night, this would have increased the demands on their ability to effectively monitor all aspects of the flight and student. The focus on monitoring other aspects of the student’s performance led them to forget to brief the student on switching to the fullest fuel tank as they had intended. Research on attention (Harrison and others, 2014) indicates that demands of competing tasks can narrow attention to the task perceived as most important at the time, reducing the likelihood of recalling or completing other intended actions.
The instructor reported that their ability to monitor the fuel status was influenced by their restricted view of the fuel gauge which was not clearly visible during a normal visual scan.
Missed opportunities by the crew to effectively monitor the fuel status led to fuel starvation and engine power loss beyond glide range of the airport. This increased the risk of having to conduct an off airfield forced landing at night.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the fuel starvation event involving Cessna T210M, VH-LLM, near Darwin Airport, Northern Territory, on 8 September 2025.
Contributing factor
Fuel was not selected to the fullest tank at all during multiple circuits resulting in a loss of power.
The student did not effectively conduct the pre-landing checks to monitor the fuel state of the aircraft, likely due to an increased workload during their first night flight in controlled airspace and the change in configuration of the primary flight display.
The instructor identified that student had not changed tanks during previous circuits however became focused on monitoring the student’s performance and did not brief the student on changing to the fuller tank.
Other factors that increased risk
The student did not conduct a visual check of the fuel quantity prior to departure, relying instead on the instructor’s recollection of sufficient fuel being available.
Sources and submissions
Sources of information
The sources of information during the investigation included:
Biernacki, M. P., & Lewkowicz, R. (2024). The role of visual conditions and aircraft type on different aspects of pilot workload. Applied Ergonomics, 118, 104268.
de Souza Borges, S. F., de Morais, P., Bovo, M. G., Castilho, D. S., & Junior, M. M. C. (2023). Evaluation of workload for operators in the aeronautical sector. Proceedings of the 33rd European Safety and Reliability Conference (ESREL 2023) Edited by Mário P. Brito, Terje Aven, Piero Baraldi, Marko Čepin and Enrico Zio
Dismukes, R. K. (2010). Remembrance of things future: Prospective memory in laboratory, workplace, and everyday settings. Reviews of human factors and ergonomics, 6(1), 79-122.
Loft, S., Tatasciore, M., & Visser, T. (2023). Managing workload, performance, and situation awareness in aviation systems. In Human factors in aviation and aerospace (pp. 171-197). Academic Press.
Harrison, T. L., Mullet, H. G., Whiffen, K. N., Ousterhout, H., & Einstein, G. O. (2014). Prospective memory: Effects of divided attention on spontaneous retrieval. Memory & Cognition, 42(2), 212-224.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the instructor
the student
the operator
Civil Aviation Safety Authority
Bureau of Meteorology.
Submissions were received from:
the instructor
the student
Bureau of Meteorology.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
About ATSB reports
ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.
Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau.
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1]Circuit: a standard flight path that aircraft follow when taking off and landing at an airfield, ensuring safe and orderly aircraft management.
[2]Local time was Australian Central Standard Time (ASCT) which is Coordinated Universal Time (UTC) + 9.30 hours.
[3]Pilot Operating Handbook: contains specific information about a particular aircraft, such as the equipment installed and weight and balance information. Manufacturers are required to include the serial number and registration on the title page to identify the aircraft to which the manual belongs
[4]Go-around: a manoeuvre where a landing approach is discontinued followed by a climb for another approach.
[5]The term ‘glass cockpit’ refers to a flat panel LCD display system that replaces the conventional analogue flight instruments in an aircraft. In this system primary flight information is presented on one or more integrated electronic flight displays.
[6]Usable fuel to reach the destination and then fly for at least 45 minutes after, at normal cruising power.
Occurrence summary
Investigation number
AO-2025-054
Occurrence date
08/09/2025
Location
Near Darwin Airport
State
Northern Territory
Report release date
28/01/2026
Report status
Final
Investigation level
Short
Investigation type
Occurrence Investigation
Investigation status
Completed
Mode of transport
Aviation
Aviation occurrence category
Engine failure or malfunction, Fuel starvation
Occurrence class
Serious Incident
Highest injury level
None
Aircraft details
Manufacturer
Cessna Aircraft Company
Model
T210M
Registration
VH-LLM
Serial number
21061937
Aircraft operator
Howard Springs Veterinary Clinic Pty Ltd
Sector
Piston
Operation type
Part 141 Recreational, private and commercial pilot flight training
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 31 May 2025 at around 12:50 EST, the pilot of an amateur‑built Van’s RV-8 aircraft was carrying out a documented flight test program to qualify the aircraft for a Special Certificate of Airworthiness in the Experimental category. The flight was being operated in the vicinity of the Jervis Bay Aerodrome, Jervis Bay Territory, when the pilot reported that during a level turn, preparing for an accelerated stall test at approximately 3,500 ft AMSL, the engine lost all power and failed. After attempts at restarting the engine were unsuccessful, the pilot was able to configure the aircraft for a glide approach and safe landing on runway 15 at Jervis Bay.
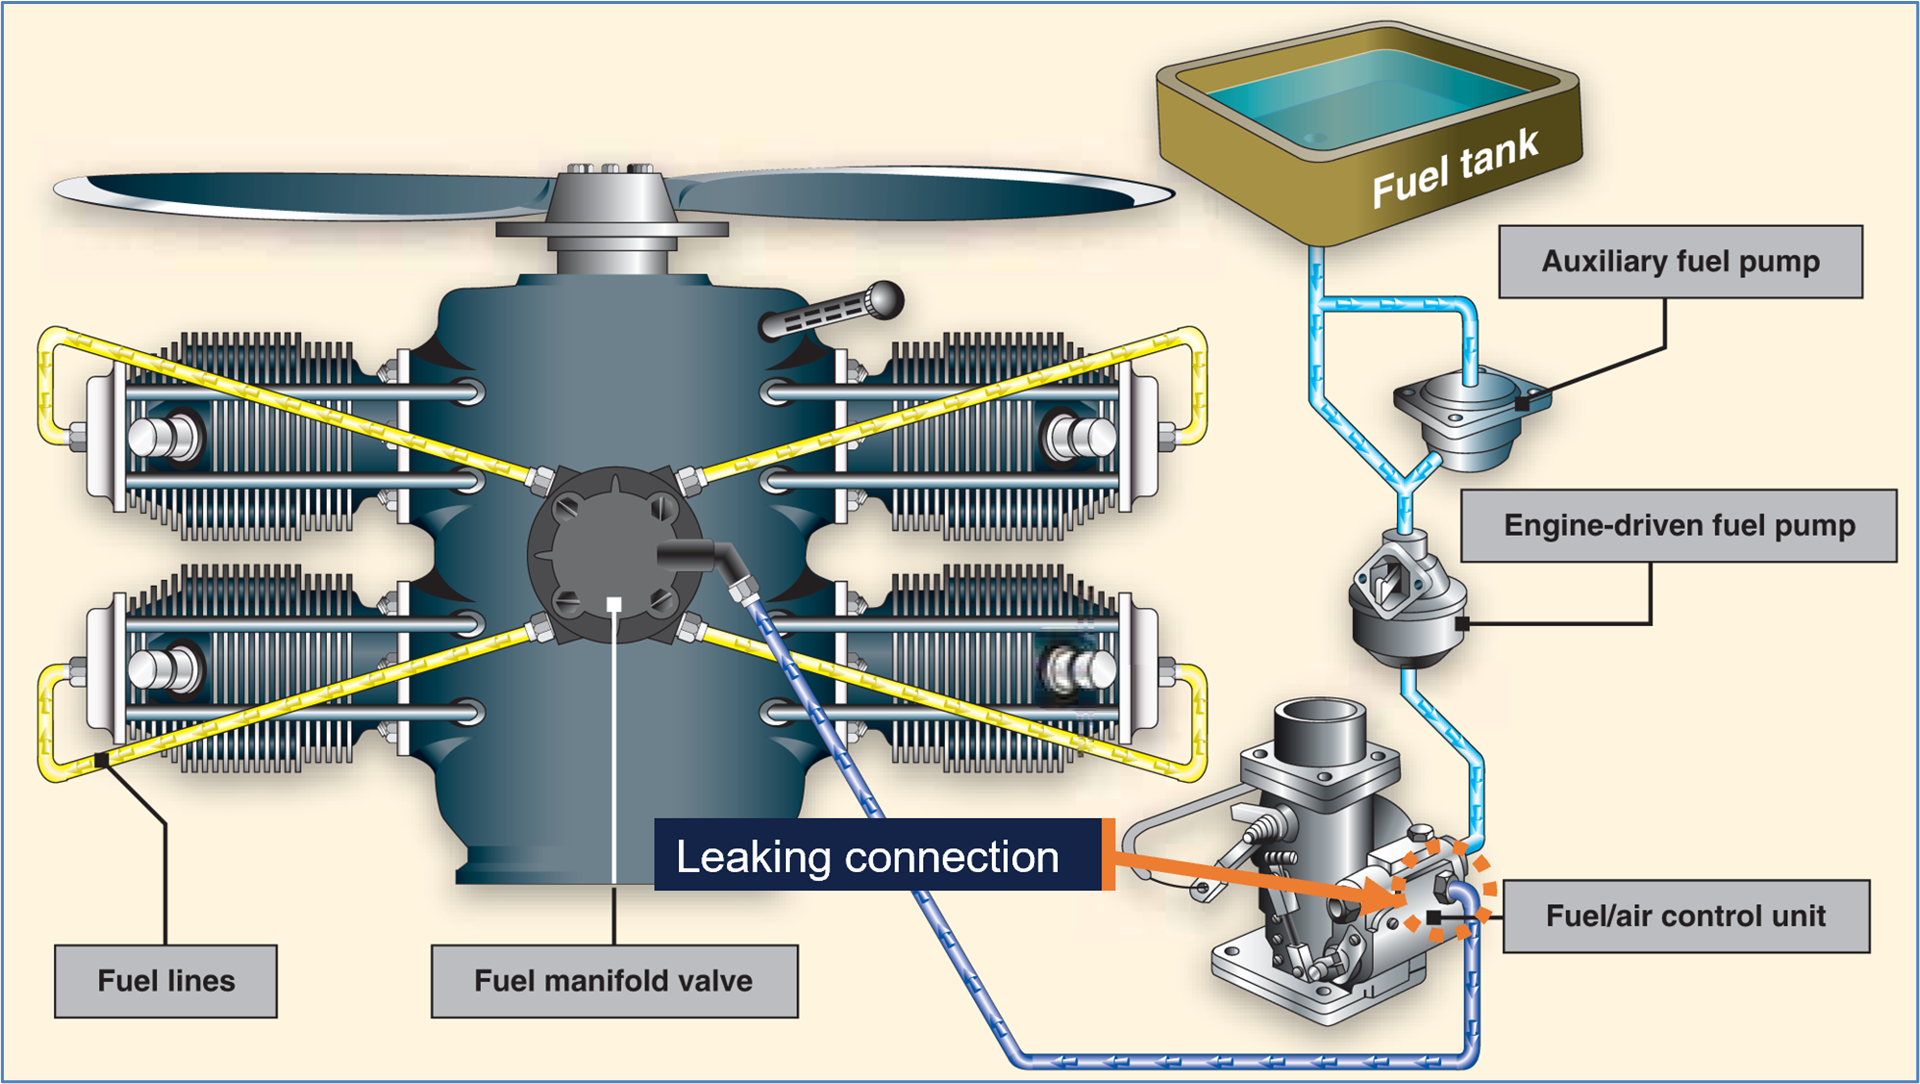
The RV‑8 aircraft was fitted with a Textron Lycoming IO‑360‑M1B four‑cylinder fuel‑injected aeronautical engine. Inspections carried out on the engine and systems after the failure identified a loose and leaking fuel connection between the fuel/air control unit (fuel servo) and the fuel manifold valve (Figure 1). A loss of integrity of the fuel line at this point would result in the engine being starved of fuel and the power loss as sustained.
The pilot reported that since the engine’s assembly in 2023 there had been no maintenance or other activity around the fuel supply connection – leading to the conclusion that the leaking fitting may have been inadequately fastened at that time.
Figure 1: IO-360 fuel system - diagrammatical illustration
An ATSB research report Amateur-built aircraft Part 2: Analysis of accidents involving VH-registered non-factory-built aeroplanes 1988-2010found that across this period, amateur‑built aircraft had an accident rate that was 3 times higher than comparable factory‑built certified aircraft conducting similar flight operations. Further, over half of the accidents were precipitated by partial or complete engine failures – these being significantly more common when compared with factory‑built aircraft.
Considering these findings, this well‑managed safety occurrence provides a direct reminder, to all pilots and crew of sports and general aviation aircraft, of the importance of being prepared for an unexpected partial or complete loss of power during any phase of flight. In this instance, the pilot’s operation at an altitude and position in respect of the Jervis Bay Airport provided some assurance of the ability to conduct a safe unpowered descent and landing after the engine failure occurred.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence summary
Mode of transport
Aviation
Occurrence ID
AB-2025-024
Occurrence date
31/05/2025
Location
Near Jervis Bay Airport
State
Australian Capital Territory
Occurrence class
Serious Incident
Aviation occurrence category
Engine failure or malfunction, Forced/precautionary landing, Fuel starvation, Fuel systems
On the morning of 5 June 2025, the pilot of a Piper Chieftain PA-31, registered VH-PGO and operated by Shine Aviation, was conducting a multi-leg return passenger transport operation from Geraldton Airport via Carnarvon Airport and Meekatharra Airport, Western Australia. After refuelling in Carnarvon, VH-PGO departed for Meekatharra with the pilot and 2 passengers on board.
The flight was being conducted under instrument flight rules. During the instrument approach to Meekatharra, the right low fuel flow warning light illuminated. Shortly after, the right boost pump inoperative warning illuminated, and the right engine commenced surging with associated aircraft yaw. The pilot performed the engine failure checks, feathered the propeller, and continued the approach. The aircraft landed without further incident.
What the ATSB found
The ATSB found that the pilot did not check that the fuel caps were secured after refuelling, as required by the pilot’s operating handbook and company procedures. This resulted in the aircraft departing with the right inboard fuel cap incorrectly secured. The incorrectly secured fuel cap led to fuel siphoning overboard in flight. Fuel siphoning overboard by airflow caused the fuel cell to collapse, resulting in the fuel tank quantity gauge overreading its contents.
The ATSB also found that the pilot was unaware of the actions to be taken on illumination of the right low fuel flow warning light and therefore did not switch tanks or crossfeed as required by the pilot’s operating handbook. This resulted in the right engine being starved of fuel during approach.
Additionally, the ATSB found that Shine Aviation's training for the PA-31 did not specifically highlight the warning in the pilot’s operating handbook or address the actions required by the pilot on the illumination of the low fuel flow warning light.
What has been done as a result
Following the occurrence, Shine Aviation reminded company pilots of the significance of the PA-31 low fuel flow warning and associated procedures. The operator also revised its training programs to strengthen coverage of abnormal and emergency scenarios, with particular emphasis on fuel system management. This included increasing the number of questions in the PA-31 theory examination. In addition, the general competency training syllabus was updated to expand instruction on fuel loading and verification processes, in‑flight fuel management practices, and aircraft type-specific emergency procedures, including detailed guidance on PA-31 annunciator panel warning lights and their operational significance.
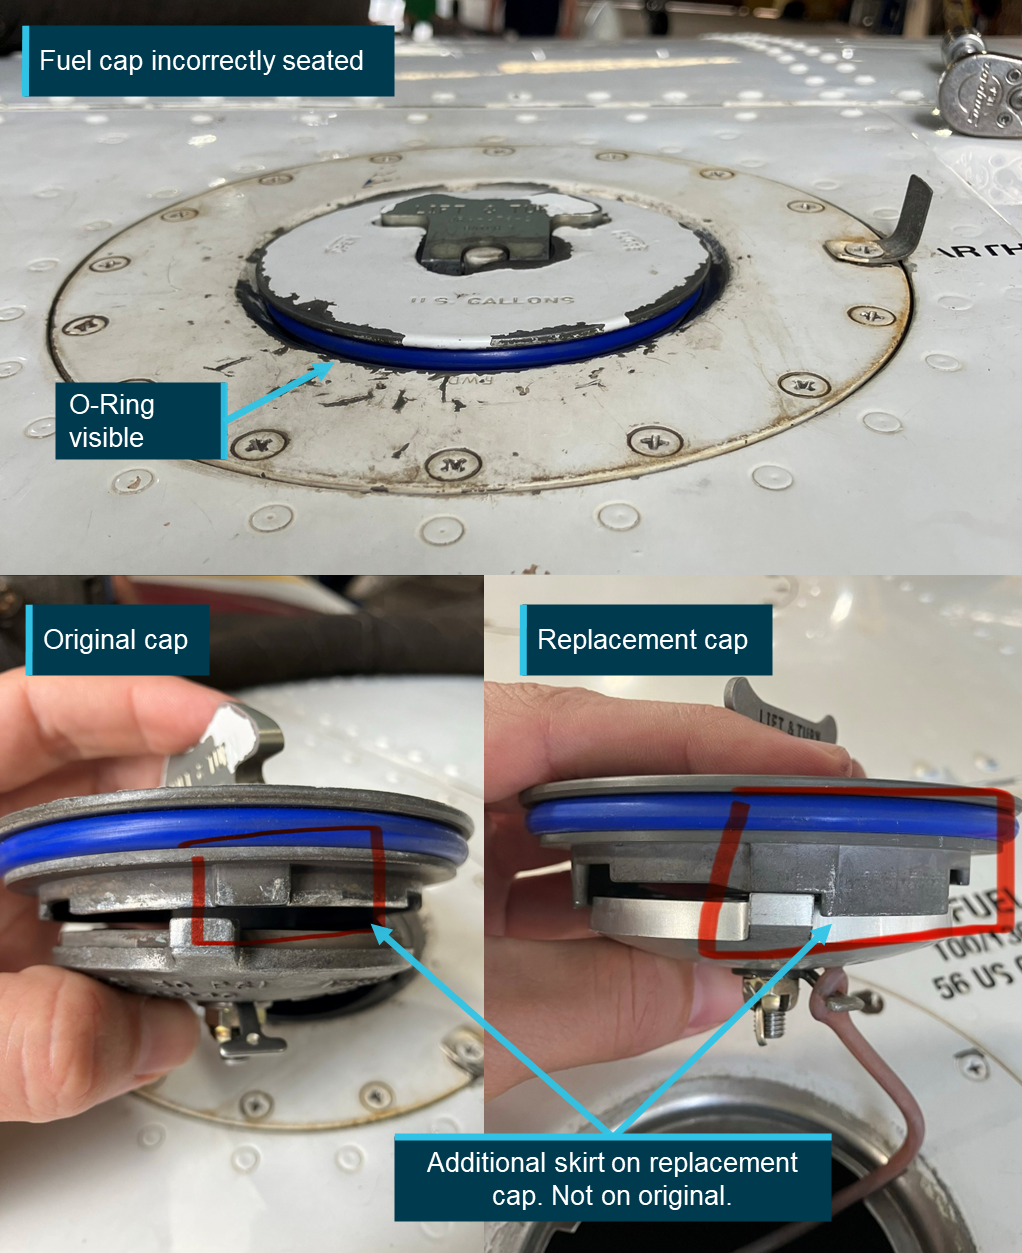
Following a repeat incorrect cap fitment in October 2025, Shine Aviation elected to replace the fuel cap as a precaution, with no further incidents reported.
Safety message
An unsecured or incorrectly installed fuel cap can result in significant fuel loss in-flight, potentially leading to an abnormal or emergency situation. Checks of fuel system security including fuel caps should be conducted by the pilot during pre-flight, turnarounds and after refuelling to ensure correct fitment. Fuel cells will collapse if tanks are not sufficiently vented when in use; a collapsed fuel cell can result in a fuel quantity gauge overreading and providing a false indication to the pilot.
Civil Aviation Safety Regulations require pilots to be competent to the standards specified for the aircraft they are operating. This includes being able to conduct all normal, abnormal and emergency flight procedures. An awareness and understanding of cautions, warnings, and limitations contained in the pilot’s operating handbook enables pilots to identify and respond to any problems that may arise, prior to them escalating further. In this case, had the pilot taken the documented action in response to the warning, it would have prevented an emergency situation arising. However, when the engine stopped during approach while in cloud, the pilot took immediate action to feather the propeller and ensure a safe landing.
Operators also play an important role in pilots achieving the competency requirements. This includes ensuring pilots receive comprehensive training that develops and reinforces aircraft specific system knowledge, particularly regarding manufacturer warnings and cautions, and decision-making skills.
CASA Advisory Circular 91-25 Fuel and oil safety provides advice and guidance on procedures and practices to ensure the safety of fuelling operations. Included in this guidance are recommendations associated with fuel caps and vents to prevent in‑flight fuel loss and starvation.
Summary video
The occurrence
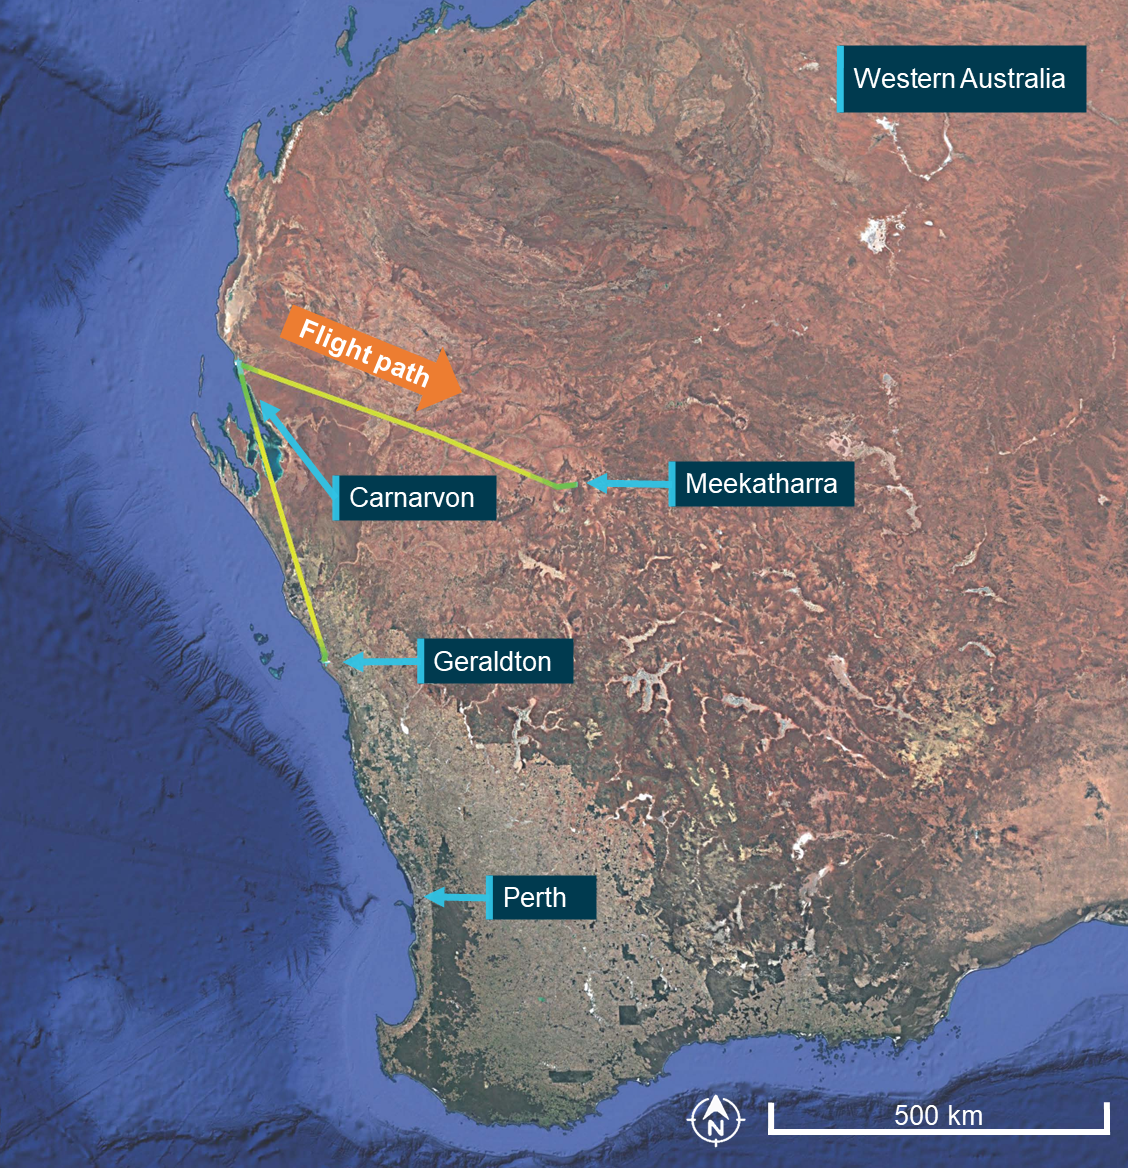
On 5 June 2025, the pilot of a Piper Chieftain PA-31-350, registered VH-PGO and operated by Shine Aviation, was conducting a multi-leg passenger transport operation under the instrument flight rules.1 At 0650 local time, the aircraft departed Geraldton Airport, Western Australia (WA), with the pilot and 3 passengers on board, and all 4 fuel tanks full – left and right, inboard and outboard. Stops were planned at Carnarvon and Meekatharra, WA, where the pilot planned to refuel, before a return flight to Geraldton (Figure 1).
Figure 1: Flight path of VH-PGO
Source: Google Earth, annotated by the ATSB
At 0817, the aircraft landed at Carnarvon Airport. The pilot then escorted the 3 passengers to the terminal building, where one passenger left the airport. The pilot returned to the aircraft to supervise refuelling and conduct a post-flight, external visual inspection of the aircraft. The local fuel supplier, on the pilot’s request, filled VH-PGO to full and then replaced the fuel caps on all 4 tanks. The refueller informed the pilot that a total of 240 L had been added to the aircraft. The pilot calculated, from the previous flight’s fuel usage, that the total fuel on board was now 688 L, which was consistent with full fuel tanks. The pilot recalled that they visually inspected but did not physically check the fuel caps for security after refuelling, and that all fuel cap latches appeared ‘down’ and in the ‘locked’ position.
The pilot assisted the 2 remaining passengers to board the aircraft, removed the chocks and then boarded the aircraft. As the pilot climbed onto the left wing to enter the aircraft, they reported giving the fuel caps ‘one last look’ and noted that they appeared correctly installed.
At 0851, VH-PGO departed Carnarvon Airport. The pilot selected the inboard fuel tanks for departure as per company and the pilot’s operating handbook (POH)2 procedures. The aircraft climbed to 9,000 ft above mean sea level (AMSL), where the pilot selected the outboard fuel tanks for the cruise to Meekatharra. At that time, the pilot calculated a fuel total of 636 L, using the onboard digital fuel flow indicator (see the section titled Fuel flow indicators). The fuel consisted of a combined 348 L in the inboard tanks and 288 L in the outboard fuel tanks. The pilot recalled that the fuel quantity gauges were indicating expected fuel quantities and fuel flow to both engines was stable throughout the take-off, climb, and into the cruise phase of flight.
During the cruise, the pilot obtained the weather at Meekatharra Airport via the aerodrome weather information service3 over VHF radio. The pilot noted that the wind was from 210° at 10 kt, cloud was overcast with a base of 800 ft above ground level (AGL), and visibility was 25 km, with no significant weather present. Based on this information, the pilot planned to conduct a landing on runway 27.4
The pilot selected the inboard tanks prior to the top of descent, in accordance with procedures. The pilot noted that the fuel quantity indication for the right inboard fuel tank was reading slightly lower than the left gauge but reported that they considered it ‘within an acceptable discrepancy for the PA-31’. The pilot calculated that 348 L remained in the inboard tanks and 118 L of fuel remained in the outboard tanks, totalling 466 L of fuel remaining on board.
The pilot descended the aircraft to 1,700 ft AGL and levelled off in accordance with the instrument approach procedure, before commencing the final approach to runway 09 with the intention of conducting a circling approach to runway 27. During this segment the R LOW FUEL FLOW warning light illuminated on the annunciator panel (see Figure 2 and the section titled Fuel system).
Figure 2: Right low fuel flow annunciator illumination during approach to Meekatharra
Source: Pilot, annotated by the ATSB
The pilot scanned the engine indications and noted they were normal, with no discrepancies between the engines. The pilot reported observing that the left and right fuel flow gauges were stable and indicating similar values, the fuel pumps were selected on, the engine mixtures were set to full rich, and the fuel boost pump circuit breakers were in and not tripped. The pilot also checked the fuel quantity gauges and stated that, while they did not recall the exact readings, nothing appeared abnormal or suggested that a tank was empty. The pilot continued the approach to Meekatharra. On the final approach segment, the aircraft entered instrument meteorological conditions (IMC).5 After entering IMC, the R FUEL BOOST INOP warning light (see the section titled Fuel system) illuminated, followed by the right engine surging and associated aircraft yaw.
The pilot conducted their memory item initial engine failure checks and feathered the right propeller. At this time, the aircraft exited IMC and was about 800 ft AGL. The pilot elected to abandon the planned circling approach to land on runway 27 and instead accepted a 5 kt tail wind to conduct a straight-in approach to runway 09, landing without further incident.
Context
Pilot information
The pilot held a Commercial Pilot Licence (Aeroplane) and an instrument rating. The pilot also held a class 1 aviation medical certificate, valid until February 2026. At the time of the occurrence, the pilot had a total flying time of 1,381 hours, with 104 hours on the PA‑31 aircraft type. The pilot had flown 47.8 hours in the last 90 days which included 45.4 hours on PA‑31 aircraft.
The pilot commenced work with the operator in January 2025 and since then, had flown approximately 250 hours, including 220 hours in multi-engine aeroplanes, prior to the occurrence.
Aircraft information
General information
VH-PGO was a Piper Aircraft Corporation PA‑313‑50, twin‑engine, 10‑seat aircraft manufactured in the United States in 1978 and first registered in June 1979. The aircraft was powered by 2 Textron Lycoming engines: a TIO‑540‑J2BD on the left and an LTIO‑540‑J2BD on the right, each driving a Hartzell 3‑bladed constant speed propeller.
Fuel system
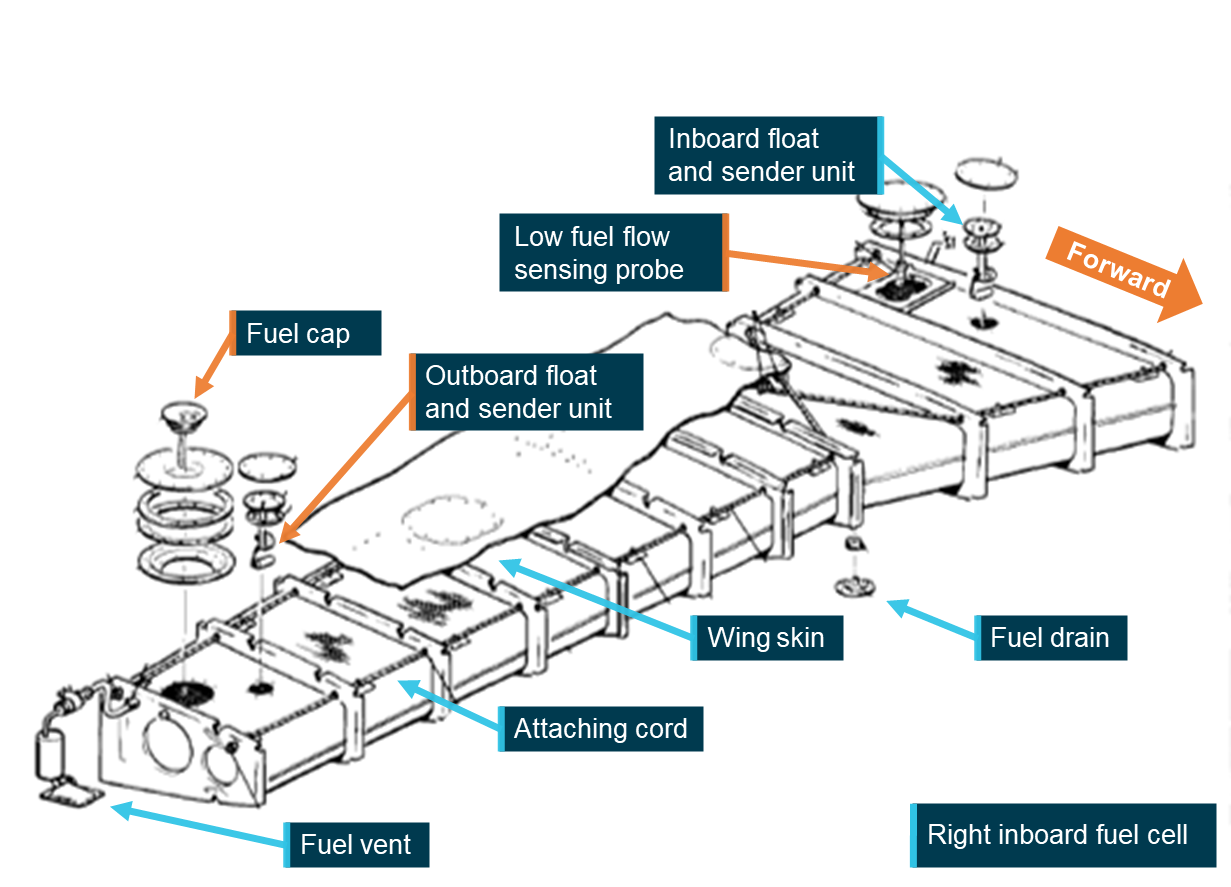
In PA-31 aircraft, fuel is stored in 4 flexible fuel cells, 2 in each wing. The fuel cell is attached to the upper inside of the wing by a cord running around the top section of the cell (Figure 3). The inboard cells hold 212 L each and the outboard cells hold 151 L each, totalling 726 L, of which 689 L are usable fuel.6
Figure 3: Right inboard fuel cell
Source: Operator, annotated by the ATSB
A fuel vent is located on each cell and is designed to maintain each tank at atmospheric pressure by allowing air to enter the tanks as fuel is consumed and as fuel volume changes with temperature and altitude. This is designed to prevent the development of a vacuum in the tanks and ensures a continuous and reliable supply of fuel to the engines. The vent also provides for slight positive pressure in flight. A restriction or blockage of the vent system can result in reduced fuel flow and fuel starvation despite usable fuel remaining in the tanks.
The fuel control panel is located at the base of the central control pedestal and contains the fuel tank selectors, fuel shutoffs and crossfeed controls. During normal operation each engine is supplied with fuel from its own respective fuel system. The fuel controls on the right control the fuel from the right cells to the right engine and the controls on the left control the fuel from the left fuel cells to the left engine. In emergencies, fuel from one system can supply the opposite engine through a crossfeed system.
Fuel is routed from the fuel cells to the selector valves where, dependent on valve position, fuel from either the inboard or outboard tank is routed to the engine. Fuel leaving the selector travels through a fuel filter, a fuel boost pump, the emergency fuel pump, a firewall shutoff valve, and then to the engine-driven fuel pump and engine fuel system.
The emergency fuel pumps are installed for emergency use in case of an engine-driven fuel pump failure. They are also used for take-off and landing and, when necessary, to prime the engines. Control switches for the emergency fuel pumps are located on the overhead switch panel to the right of the fuel gauges.
Two electric fuel quantity gauges are also mounted on the overhead switch panel (Figure 5). These indicate the fuel tank level from float-style sender units in each tank. The gauges indicate left inboard or outboard tank, and right inboard or outboard fuel tank quantities dependent on selector valve position. The inboard tanks contain 2 sender units each, one near the wing root and one near the filler cap (Figure 3).
The fuel boost pumps are operated continuously and are provided to maintain fuel under pressure to the engine‑driven fuel pump. There are no fuel boost pump control switches or pressure gauges.
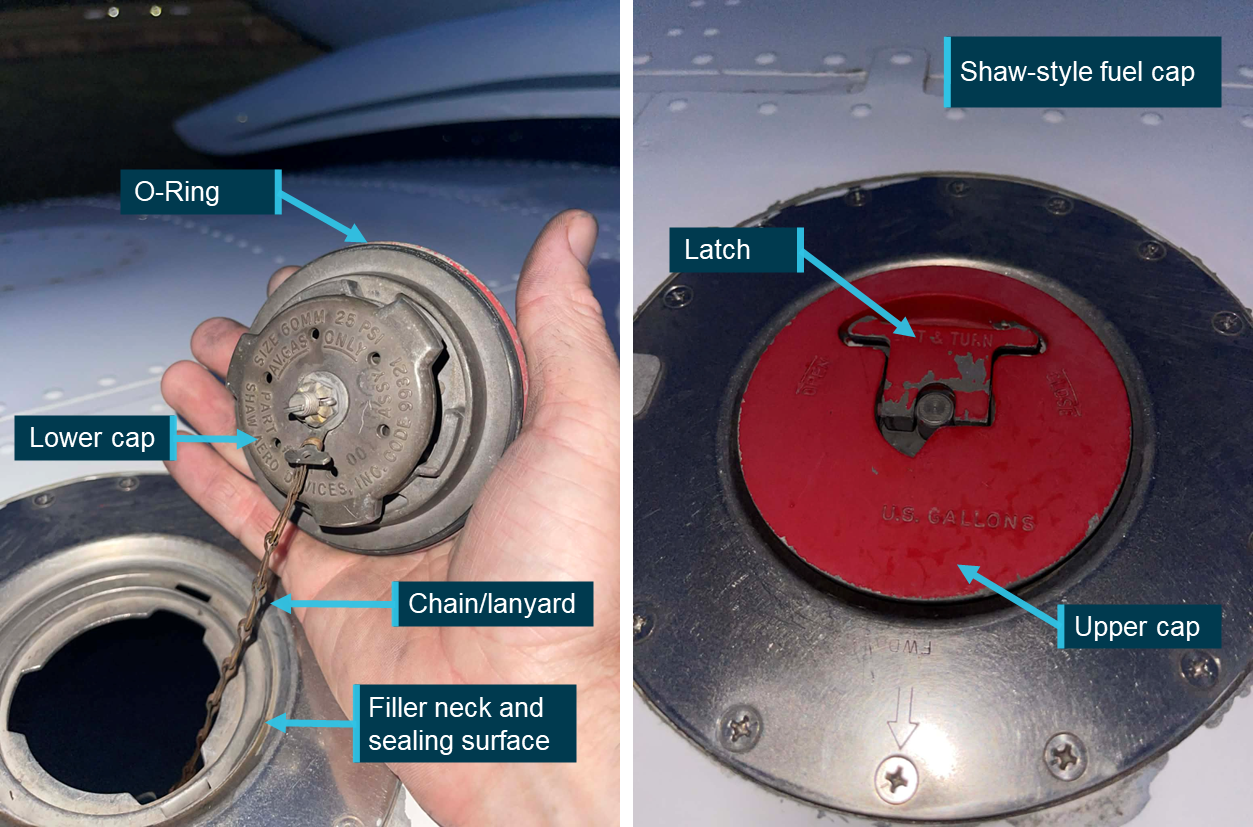
Each tank has a separate Shaw-style fuel cap for servicing (Figure 4). The inboard tank caps are located on the upper centre section of each wing and the outboard tank caps are on the upper outboard section of each wing. The right inboard fuel cap is not visible from the pilot’s seated position. The fuel caps are installed on the filler neck of each tank and utilise a twist‑to‑lock cam mechanism. As the latch is rotated, the upper and lower sections are drawn together, compressing the O‑ring seal against the filler neck to form a secure, fuel- and water-tight closure. The lower cap lugs engage under the filler neck flange to hold the cap in place against vibration, pressure changes, and airflow that is encountered in flight. The caps are also attached to the wing by a lanyard.
Figure 4: Shaw-style fuel cap
Source: Toby Dorn, annotated by the ATSB
Fuel flow indicators
Analogue fuel flow gauges located on the instrument panel indicate fuel flow to the engines in US gallons per hour. An FS-450 fuel flow indicator is also located on the instrument panel and digitally displays real-time fuel flow in litres per hour, fuel used, fuel remaining, and time-to empty. It is used to assist pilots in fuel management, however, it records fuel flowing through the fuel flow indicator transducer into the engine fuel system and would not detect a leak upstream such as a fuel tank leak.
Fuel system warning lights
Right and left fuel flow warning lights are mounted on the annunciator panel and illuminate to warn the pilot of an impending fuel flow interruption from the inboard tanks. The lights are activated by a probe that is mounted near each inboard fuel tank outlet (Figure 3). In the event of the fuel level near the tank outlet dropping to a point where a fuel flow interruption could occur, the LOW FUEL FLOW warning light will illuminate.
The pilot’s operating handbook contains the following warning:
WARNING
If either the right or left fuel flow warning light illuminates and the fuel gauge indicates fuel remaining in the corresponding inboard tank, this will indicate a malfunction of the flapper door in the inboard tank. Immediately select the outboard tank or select crossfeed to avoid fuel flow interruption.
This warning indicates a possible flapper door malfunction within the inboard fuel tank.7 In this condition, the fuel flow warning light may illuminate despite sufficient fuel remaining in the affected tank, as the malfunction may restrict fuel flow to the tank outlet. The procedure directs the pilot to immediately select the outboard tank or crossfeed to maintain fuel supply and prevent fuel flow interruption.
Left and right FUEL BOOST PUMP INOP warning lights are also mounted on the annunciator panel, and they illuminate when the fuel boost pressure to the associated engine fuel pump is less than 3 PSI. An illumination of a fuel boost pump inoperative warning light will occur immediately prior to that engine being starved of fuel.
Post‑occurrence
Pilot actions
After landing and shutting down the left engine, the pilot escorted the passengers to the terminal, reported the occurrence to Shine Aviation, and then returned to the aircraft. The pilot then applied battery power and noted that the right inboard tank fuel quantity gauge was indicating just above a quarter full, and the left inboard tank fuel quantity gauge was indicating half a tank (Figure 5). The pilot recalled that this was unusual and was more significant than the minor discrepancy observed at the top of descent.
Figure 5: Inboard tank quantity discrepancy after landing
Source: Pilot, annotated by the ATSB
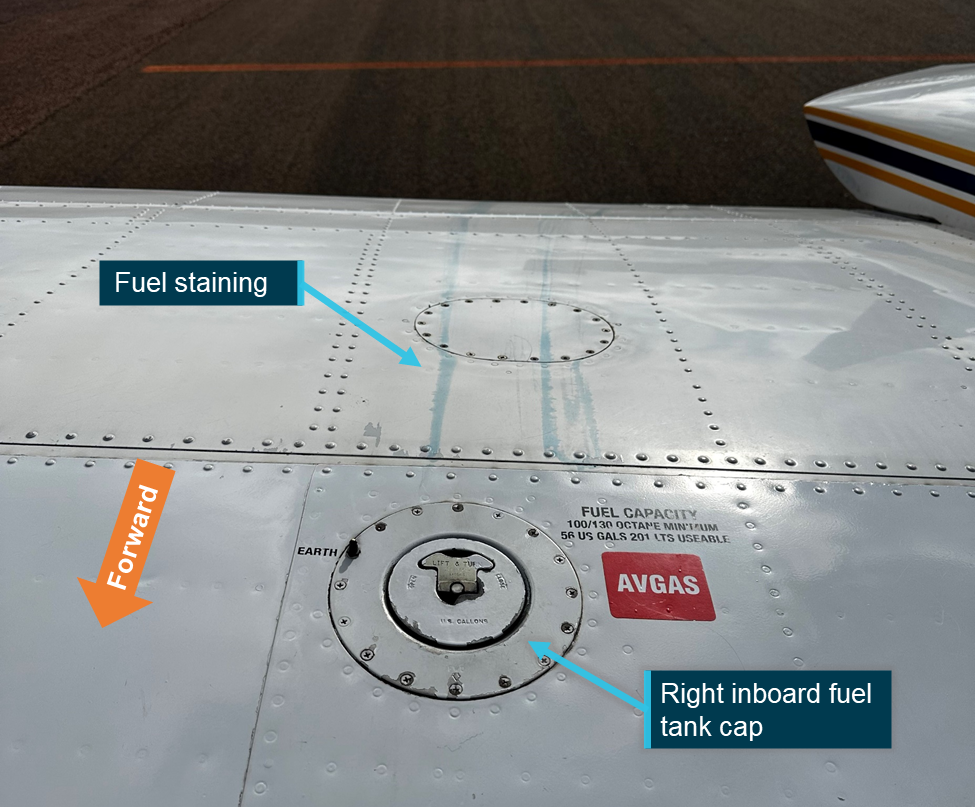
The pilot then conducted a visual inspection of the right wing area and noted blue fuel streaks behind the right inboard fuel cap (Figure 6). After attempting to drain fuel out of the right inboard fuel tank without success, the pilot then removed the right fuel cap to see if any fuel was present. The pilot noted that the fuel cap latch was ‘extremely’ difficult to unlatch and required the use of both hands. Upon looking in the tank, the pilot observed that it was empty, and the bottom of the fuel cell had been sucked up towards the fuel filler area. The pilot then reinstalled the cap, commenting that the cap latched normally and without difficulty.
Figure 6: Fuel staining aft of right inboard fuel cap
Source: Pilot, annotated by the ATSB
At hourly intervals, the pilot reapplied battery power noting that it took 2.5 hours after landing for the right inboard tank fuel gauge to read zero.
Engineering inspection
The company’s chief engineer arrived about 3.5 hours after the occurrence to commence troubleshooting. They reported that there was no evidence of a leak source around the right inboard fuel tank aside from the fuel staining aft of the fuel cap. Although the pilot had already removed and refitted the fuel cap, an inspection of the fuel cap was conducted with no defects noted including the O‑ring being found serviceable. The chief engineer replaced the cap O‑ring seal and re-tensioned the cap’s latch mechanism as a precaution. They also commented that there was a possibility of the fuel cap lanyard interfering with the cap’s fitment however no damage to the cap or the lanyard was identified.
The chief engineer observed that the bottom of the fuel cell had been drawn up towards the fuel cap and required manual reseating. They filled the inboard tanks to maximum capacity; 67 L was required to fill the left inboard tank, and 204 L was required to fill the right inboard tank. The chief engineer stated that they were satisfied that the fuel cell had reseated correctly within the fuel tank cavity.
The engines had been operated alike up to the right engine starvation. The ATSB estimated that the left engine consumed 6 L of fuel after the right engine stopped. Therefore, about 131 L had been siphoned and lost overboard from the right tank through the fuel cap during flight.
During the draft report review process, the ATSB was informed of a repeat incorrect fitment of VH-PGO’s right inboard fuel cap that resulted in fuel leaking during flight. The operator advised that this occurred on 6 October 2025, 4 months and an estimated 60–70 refuels after the initial occurrence. However, the chief engineer was able to observe the cap in its incorrectly fitted state where they determined that the cap had not been seated correctly prior to being latched. This resulted in the upper and lower portions of the cap clamping on the filler neck of the wing (Figure 7). Following the second occurrence, the chief engineer elected to replace the fuel cap as a precaution.
Upon receipt of the new fuel cap the chief engineer noted that a skirt had been incorporated into the design of the replacement cap therefore limiting the ability of the upper and lower portions of the cap to clamp on the filler neck of the wing (Figure 7). The ATSB contacted the manufacturer for further information on the apparent design change. However, at the time of publication no response had been received.
Figure 7: Incorrect fitment on 6 October 2025
Source: Operator, annotated by the operator and the ATSB
Flight testing
Followingthe inspection, the aircraft was ferried back to Geraldton (without passengers) by the head of flying operations, with the chief engineer seated in a position that allowed full view of the right inboard fuel tank cap.
During climb out of Meekatharra Airport, they observed that the FS-450 fuel flow indicator for the right engine was displaying a significantly lower fuel flow than expected for the selected power and mixture setting, and it was lower than the corresponding analogue fuel flow gauge. The FS-450 indicated approximately 70 L/h, compared to the expected value of about 120‑L/h. However, the right engine exhaust gas temperatures, oil temperature, manifold pressure and cylinder head temperature were within normal limits for that power setting and comparable to the left engine. On that basis, they assessed that the FS‑450 indication was erroneous and not representative of the actual fuel flow to the engine, with the chief engineer stating that the engine would not be able to run with that fuel flow for that power setting. The engineer advised the head of flying operations to use the analogue fuel flow gauges for engine management for the remainder of the flight.
The occurrence pilot reported that they had not observed any irregularities with any of the engine indications prior to the occurrence. This was supported by a review, conducted by the operator’s head of safety and quality assurance, of VH‑PGO’s previous 8 flight logs, which found that fuel usage data was normal and within acceptable parameters for the PA‑31‑350.8 In addition, a review of the flight logs for flights conducted after the occurrence identified no abnormalities.
The chief engineer later commented that the FS‑450 unit’s calibration may have been inadvertently altered by the occurrence pilot after the event during their initial troubleshooting.
During the return flight to Geraldton, the chief engineer did not observe any fuel leaking from the right inboard fuel tank cap, and a post‑flight inspection confirmed that no fuel leakage was present. The aircraft was subsequently flown that evening and the following morning, with no further leaks or related issues identified.
Refueller
The refueller who uplifted fuel to the aircraft at Carnarvon and secured the fuel caps before the occurrence flight later recalled that the right inboard fuel cap was slightly difficult to close. However, based on their familiarity with the aircraft, they believed the cap was properly secured. They also stated that if they had any concerns about the aircraft, they would have informed the pilot.
Pre-flight and refuelling
The pre-flight inspection detailed in the POH stated that the fuel supply should be checked visually, and a check was required to ensure the fuel caps are securely in place. To visually check the fuel supply, the cap would have to be removed and therefore a physical check of security is performed when the caps are installed.
Shine Aviation’s Policy and Procedures manual provided instructions regarding refuelling and fuel caps, additional to the POH procedures. The instructions included:
When fuelling is complete, sufficient airspace must remain in each fuel tank to allow for anticipated fuel expansion, and the PIC must ensure that all fuel and oil tank caps have been securely refitted.
PA-31 training
Regulatory requirements
Shine Aviation operated as a Civil Aviation Safety Regulation (CASR) Part 135 operation (Australian Air Transport Operations - Smaller Aeroplanes) and held a Part 135 Air Operator’s Certificate (AOC). Section 12.05 of the Part 135 Manual of Standards stated the following:
• The flight crew member must have successfully completed the operator’s conversion training, and flight crew member proficiency check, for the aeroplane.
• The training must deal with the following:
- training in the duties and responsibilities for the flight crew member’s position;
- training in the standard operating procedures for the type or class of aeroplane used for the flight;
- training in the normal, non-normal and emergency procedures for an aeroplane of that type or class;
- training in any flight procedures or manoeuvres, conducted in an aeroplane of that type or class, for which the operator holds an approval under regulation 91.045, or 135.020, of CASR;
Note: Examples of approvals issued under regulation 91.045, or 135.020, of CASR include approvals to conduct low visibility operations and flights using certain PBN navigation specifications.
- training in the procedures for any other operations conducted by the operator in an aeroplane of that type or class that the flight crew member has not previously experienced, for example, precision runway monitor operations or land and hold short operations.
Under CASR Part 61.385 Limitations on exercise of privileges of pilot licences – general competency requirement, a pilot may only exercise the privileges of their licence if they are competent to the standards specified for the relevant aircraft they are operating. This includes being able to conduct all normal, abnormal and emergency flight procedures for that aircraft.
Company flight training
Shine Aviation was approved by CASA as a CASR Part 141 training organisation, enabling it to conduct in-house pilot training and competency assessments in support of pilot qualification for operations under the organisation’s Part 135 Air Operator’s Certificate.
Pilots underwent conversion training onto company aircraft in 2 parts: a ground-based theory component, followed by a flying component. The ground-based theory component consisted of self-paced study of the POH prior to undergoing a multiple-choice theory exam. The theory examination consisted of 25 PA-31 specific questions, automatically generated from a question bank of 82, including topics relating to weight and balance, aircraft performance, and systems knowledge.9
The flying component involved the pilot conducting 2 non-revenue (no passengers) training flights with a company flight instructor. Shine Aviation’s General Competency Training syllabus included the following competencies for the pilots to demonstrate:
departure and arrival (including appropriate engine management for turbocharged aircraft)
stalling
steep turning
different cruise configurations
upper air asymmetric where applicable
normal circuit
flapless circuit
crosswind circuit
engine failure on take-off
engine failure elsewhere in circuit
single engine go‑around
discussion on differences in standard practice between engine models (oil uplift, engine monitoring etc)
any other multi engine or single engine class rating competencies as deemed necessary by instructor.
Although this syllabus contained specific competencies for other types of aircraft Shine Aviation operated, it did not contain any specific PA-31 competencies. However, it did contain an ‘underpinning knowledge’ section in which ‘Instrument failure and warning systems fitted to the aeroplane’ was listed.
Following satisfactory demonstration of the required flying competencies, the pilot was required to act as a copilot for approximately 30 hours of normal company operations prior to conducting single pilot operations.
The pilot in this occurrence completed their ground component and 2 non-revenue training flights, involving 3 hours of flight and 4 hours of briefing time, in January 2025. The pilot then conducted approximately 30 hours of flying as a copilot in the PA-31, including 13.5 hours in VH-PGO, prior to being assessed and approved for single pilot operations. The pilot completed an instrument proficiency check in January 2025 in the PA-31 with a company examiner.10
In May 2025, the pilot successfully completed 2 recurrent flight training exercises in the company’s approved synthetic training device.11 These exercises involved various emergency and abnormal scenarios consisting of adverse weather, engine failures, single engine approaches, instrument failures and flight planning exercises.
Training regarding low fuel flow warning light
The theory examination contained the following question related to the LOW FUEL FLOW warning light:
Illumination of a LOW FUEL FLOW annunciator:
a) Indicates that outboard fuel quantity has decreased to a point where engine power loss could occur
b) Indicates low fuel quantity in the inboard tanks
c) Indicates that a fuel boost pump has failed
d) a and c
The correct answer is (b), however this question pertains to the function of the warning light but does not cover the published warning or the actions to be taken by the pilot upon its illumination (see the section titled Fuel system warning lights). Regardless, the theory examination that was generated for the occurrence pilot did not include this question.
Shine Aviation’s head of training for the PA-31 stated that the LOW FUEL FLOW warning light was likely discussed during the flight training component when the annunciator panel was covered. However, they also stated that not every annunciator panel indication was examined in detail.
The incident pilot advised that the LOW FUEL FLOW warning light was not specifically addressed during initial or copilot training and that, although they understood that it related to a fuel flow issue to the affected engine, they were not aware of, or could not recall, the required immediate actions that are directed by the warning in the POH.
Related occurrences
Excluding the incident flight, the ATSB occurrence database contained 49 reported occurrences of fuel leaking or venting from a fuel cap on non-jet aircraft between 2014 and 2025. Of those occurrences, 8 resulted in fuel starvation or fuel exhaustion. Those numbers likely under‑represent the total number of incidents of this type, as the ATSB only required instances of fuel leaking/venting or missing/insecure fuel caps to be reported for commercial passenger transport operations.
ATSB occurrence brief AB-2021-009 was published following a fuel starvation event involving a PA-31-350 in 2021:
On 21 March 2021 a Piper PA-31-350 aircraft was operating a scheduled freight flight from Moorabbin, Victoria to Devonport, Tasmania. During approach, the low fuel flow and low boost pump warning lights illuminated. The right engine stopped shortly after. The pilot in command confirmed the fuel selector was in the correct position and observed that the fuel gauges indicated three-quarters full, which was as expected. The pilot then attempted to cross-feed fuel from the left engine, which was unsuccessful. By this time, the aircraft was on mid-final and, once assured of making the runway, the pilot stopped troubleshooting and concentrated on landing the aircraft.
After landing, the pilot inspected the fuel cap, which appeared to be secured correctly. However, blue stains were evident on top of the wing consistent with fuel venting out of the fuel cap. The fuel system was subsequently inspected by maintenance personnel with nil defects found with the fuel cap and no blockages in the fuel tank vents.
The pilot later advised that the rubber bladder containing the fuel within the tank was sucked up against the top of the wing as the tank emptied, providing a false indication of the fuel remaining in the tank.
ATSB occurrence investigation AO-2024-008 was published following a fuel exhaustion event in 2024:
On 8 March 2024, the pilot of an Aero Commander 500-S, registered VH-MEH and operated by GAM Air, was conducting a return cargo transport operation from Bankstown Airport to Parkes Regional Airport, New South Wales with one intermediate stop outbound, and 2 intermediate stops on return.
After landing on the first sector, the pilot found the fuel cap was off and secured only by a retention chain. The pilot re-secured the cap but after landing at Parkes on the second sector, they again found the fuel cap off. They arranged an inspection by a maintenance engineer, where a fault was found that prevented the fuel cap from locking and rectified it.
Later that day, the pilot commenced the return sectors to Bankstown. Shortly after departing Bathurst for the final sector, both engines lost power, and the pilot conducted a forced landing in a field. The aircraft was undamaged and the pilot was uninjured.
The ATSB found that the fuel cap retention chain had lodged within the fuel tanks anti siphon valve. This allowed fuel to be siphoned overboard during flight.
CASA Advisory Circular 91-25 Fuel and oil safety, section 6, highlighted recommendations associated with fuel caps and vents. In particular, the circular advised of the possibility of fuel siphoning overboard due to a cap attachment chain or lanyard becoming trapped across a fuel cap seal. The advisory circular also identified that an insufficiently vented tank may collapse the fuel bladder and exaggerate indications of fuel within the tank.
Safety analysis
Introduction
On 5 June 2025, the pilot of a Piper Chieftain PA-31, registered VH-PGO, and operated by Shine Aviation, was conducting a passenger transport operation from Carnarvon to Meekatharra, Western Australia. During the approach to Meekatharra Airport, the R LOW FUEL FLOW warning light illuminated, followed shortly by the R FUEL BOOST INOP warning light and surging of the right engine. The pilot conducted their memory item initial engine failure checks and feathered the right propeller. The pilot continued the approach and landed without further incident.
Fuel siphoned overboard
Photographs taken by the pilot after landing at Meekatharra Airport show fuel staining immediately aft of the right inboard fuel cap, consistent with fuel leaking from the cap in flight. This staining, in conjunction with the pilot’s observation that the right inboard tank was emptied earlier than expected based on calculated consumption, and that the tank cell collapsed upwards towards the cap, all indicate that fuel had likely been siphoned through the cap in flight. The pilot also reported that the fuel cap latch was difficult to lift, suggesting the cap may not have been correctly seated.
During the post-occurrence inspection, the chief engineer found no evidence of any other fuel leaks around the right inboard tank. The pilot had removed and reinstalled the cap prior to this inspection, therefore the chief engineer could not determine exactly how the cap was incorrectly fitted. The chief engineer was also unable to reproduce an incorrect installation. However, the chief engineer considered it likely that the fuel cap had been incorrectly secured, including the possibility of the attaching lanyard interfering with the cap and seal. No damage was observed to the cap, seal, or lanyard and the chief engineer replaced the O-ring on the cap as a precaution, although they considered the removed O‑ring serviceable. Subsequent flights, including the immediate post‑occurrence flight with the chief engineer observing the cap, did not reproduce the leak. As the leak did not recur, it was almost certain the fuel cap was incorrectly secured in Carnarvon.
As part of the troubleshooting, the chief engineer refuelled the right inboard tank with 204 L, while the left tank required only 67 L to fill. Given that both tanks had been selected for use at similar times during the flight, and accounting for fuel used by the left engine after the right had stopped, the discrepancy indicated that approximately 131 L of fuel had been lost through the fuel cap from the right inboard tank.
Contributing factor
The fuel cap on the right inboard fuel tank was almost certainly incorrectly secured which led to fuel being siphoned overboard in flight.
Fuel cap installation
Shine Aviation’s Policy and Procedures manual required the pilot in command to ensure that fuel caps were securely fitted. While this did not explicitly require the pilot to remove and reinstall the caps, the pilot’s operating handbook specified that the pilot in command must visually check the fuel supply and confirm that the fuel caps are secure. Checking the fuel quantity required the pilot removing the caps and physically handling the fuel caps to verify correct fitment.
Although the pilot stated that they visually inspected the fuel cap, a closer inspection or physical check of the cap would likely have aided the pilot in identifying the incorrect installation. Consequently, the pilot did not detect that the right inboard fuel tank cap was incorrectly secured.
Contributing factor
The pilot did not check that the fuel caps were secured as required by the pilot’s operating handbook and company procedures, resulting in the aircraft departing with the right inboard fuel cap almost certainly incorrectly secured.
False gauge reading
During flight, the rate of fuel being siphoned through the fuel cap was likely sufficient to overcome the vent’s ability to equalise pressure in the fuel tank. This resulted in negative pressure collapsing the fuel cell as observed by both the pilot and the chief engineer during their post-occurrence inspections. As the fuel cell was secured by a single cord around the upper perimeter, the collapse of the fuel cell resulted in the base of the cell lifting towards the filler port.
As one of the right inboard fuel tank float-style sender units was located near the fuel filler port, it is likely that the upwards lifting of the fuel cell floor toward the filler port, raised the outboard sender unit’s float. This resulted in an overreading of the cockpit fuel quantity gauge. ATSB occurrence brief AB-2021-009 identified a similar failure mechanism where the fuel cell collapsed resulting in the fuel gauge overreading its contents. The Civil Aviation Safety Authority’s advisory circular (AC) 91-25 Fuel and oil safety, section 6, also contained information about collapsing fuel cells interfering with the accuracy of fuel gauge readings.
During the subsequent flight, the onboard fuel flow indicator was incorrectly and significantly underreading the right engine fuel flow. However, the pilot reported it was functioning normally during the flight to Meekatharra. Engineers assessed the instrument had probably been inadvertently recalibrated during post-incident fault finding.
When the pilot changed from the outboard tanks to the inboard tanks at the top of descent, they noticed that the right inboard tank quantity gauge was reading a slightly lower quantity than the left inboard, however they assessed that this was an acceptable discrepancy related to VH-PGO. It is likely that the right inboard tank was almost empty at that stage of flight as the R LOW FUEL FLOW warning light illuminated shortly after.
Contributing factor
Fuel siphoning overboard by airflow caused the fuel cell to collapse, resulting in that fuel tank quantity gauge overreading its contents.
Response to warning
The warning in the pilot’s operating handbook (POH) stated that if the right or left LOW FUEL FLOW warning light illuminated, and the fuel gauge indicated fuel remaining in the corresponding inboard tank, this indicated a malfunction of the flapper door in the inboard tank. The prescribed action was to immediately select the outboard tank or select crossfeed to avoid fuel flow interruption. While a flapper door malfunction did not occur in this instance, compliance with the warning actions would likely have restored fuel supply.
The pilot was unaware of the required immediate actions and therefore did not respond to the R LOW FUEL FLOW warning light as directed by the POH. The pilot was also unaware that a fuel starvation event was developing, until the subsequent illumination of the right FUEL BOOST INOP warning light and associated engine surging.
The sequential activation of the R LOW FUEL FLOW warning followed by the right FUEL BOOST INOP warning was a progressive indication that fuel flow to the right engine would be interrupted. As the pilot did not restore fuel flow following either warning, the right engine became starved of fuel, resulting in the engine surging and a corresponding yaw of the aircraft.
Contributing factor
The pilot was unaware of the actions to be taken on illumination of the LOW FUEL FLOW warning light and therefore did not switch tanks or crossfeed as required by the pilot’s operating handbook. This resulted in the right engine being starved of fuel during approach.
Training regarding low fuel flow warning light
As part of the Civil Aviation Safety Regulations (CASR) limitations on the privileges of a pilot licence, pilots were required to be competent in conducting all normal, abnormal and emergency flight procedures for the aircraft. This required the pilot to be aware of the POH warnings and associated instructions included in emergency procedures. Additionally, under CASR Part 135, operators were also required to ensure that flight crew were trained in the normal, non-normal and emergency procedures for the aircraft they were operating.
Shine Aviation PA-31 pilots independently studied the POH and subsequently undertook a theory examination. This examination consisted of 25 PA-31 specific questions that were automatically generated from a question bank of 82. Although there was one question regarding the illumination of the LOW FUEL FLOW warning light, this question did not evaluate the immediate response required. Furthermore, this question was not included in the occurrence pilot’s automatically generated examination.
Shine Aviation’s head of PA-31 training advised that the LOW FUEL FLOW annunciator and associated warning were likely addressed to some extent during practical line training. However, the occurrence pilot did not recall this topic being covered. Shine Aviation’s General Competency syllabus required a general knowledge of the warning systems, however, it did not specifically require demonstration of the appropriate response to a LOW FUEL FLOW warning. In this case, the training was ineffective at ensuring the incident pilot was competent in responding to the warning.
Contributing factor
Shine Aviation's training for the PA-31 did not specifically highlight the warning in the pilot’s operating handbook or address the actions required by the pilot on the illumination of the low fuel flow warning light. (Safety issue)
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the fuel starvation involving Piper PA-31, VH-PGO, 28 km west of Meekatharra Airport, Western Australia, on 5 June 2025.
Contributing factors
The fuel cap on the right inboard fuel tank was almost certainly incorrectly secured which led to fuel being siphoned overboard in flight.
The pilot did not check that the fuel caps were secured as required by the pilot’s operating handbook and the company procedures, resulting in the aircraft departing with the right inboard fuel cap almost certainly incorrectly secured.
Fuel siphoning overboard by airflow caused the fuel cell to collapse, resulting in that fuel tank quantity gauge overreading its contents.
The pilot was unaware of the actions to be taken on illumination of the LOW FUEL FLOW warning light and therefore did not switch tanks or crossfeed as required by the pilot’s operating handbook. This resulted in the right engine being starved of fuel during approach.
Shine Aviation's training for the PA-31 did not specifically highlight the warning in the pilot’s operating handbook or address the actions required by the pilot on the illumination of the low fuel flow warning light. (Safety issue)
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Low fuel flow warning light and subsequent actions not highlighted in training
Safety issue description: Shine Aviation's training for the PA-31 did not specifically highlight the warning in the pilot’s operating handbook or address the actions required by the pilot on the illumination of the low fuel flow annunciator light.
Glossary
AMSL
Above mean sea level
AGL
Above ground level
CASA
Civil Aviation Safety Authority
CASR
Civil Aviation Safety Regulations
IFR
Instrument flight rules
IMC
Instrument meteorological conditions
POH
Pilot’s Operating Handbook
Sources and submissions
Sources of information
The sources of information during the investigation included:
the pilot
the operator of VH-PGO
Civil Aviation Safety Authority
Airservices Australia.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the pilot
the operator of VH-PGO
Civil Aviation Safety Authority.
Submissions were received from:
the pilot
the operator of VH-PGO.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
About ATSB reports
ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.
Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau.
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
^Instrument flight rules (IFR): a set of regulations that permit the pilot to operate an aircraft in instrument meteorological conditions (IMC), which have much lower weather minimums than visual flight rules (VFR). Procedures and training are significantly more complex as a pilot must demonstrate competency in IMC conditions while controlling the aircraft solely by reference to instruments. IFR-capable aircraft have greater equipment and maintenance requirements.
^Pilot’s operating handbook: a manufacturer-produced manual that provides pilots with all the essential information needed to safely operate the aircraft.
^Aerodrome weather information service (AWIS): actual weather conditions, provided via telephone or radio broadcast, from Bureau of Meteorology (BoM) automatic weather stations, or weather stations approved for that purpose by the BoM. Winds are in degrees magnetic.
^Runway number: the number represents the magnetic heading of the runway to the nearest 10 degrees.
^Instrument meteorological conditions (IMC): weather conditions that require pilots to fly primarily by reference to instruments, and therefore under instrument flight rules (IFR), rather than by outside visual reference. Typically, this means flying in cloud or limited visibility.
^Usable fuel: the amount of fuel in a fuel tank that can reliably be supplied to the engine in all operating conditions. This excludes fuel that cannot be used due to aspects such as tank geometry and fuel pickup locations.
^A flapper door is installed in each inboard tank to keep fuel around the tankoutlet by preventing it from flowing away during manoeuvring, climb, descent, turbulence, or uncoordinated flight.
^The pilot records fuel quantity prior to start, fuel quantity used via the FS-450, and fuel quantity after shutdown for each sector in a flight log. This allows the operator to monitor fuel usage for individual aircraft.
^Following the occurrence, Shine Aviation increased the number of questions in the PA-31 theory examination to 30.
^Instrument proficiency check (IPC): A required annual flight test to ensure that a pilot maintains the necessary skills and knowledge to safely operate an aircraft under instrument flight rules (IFR). It involves demonstrating competency in tasks such as navigation, communication, and handling the aircraft in various conditions, all while relying on instruments rather than visual references.
^Recurrent training: Shine Aviation conducts recurrent training for all its instrument rated pilots every 6 months. Training is delivered in a synthetic flight training device and consists of simulated IFR flights that include operational and decision-making scenarios tailored to the individual pilot. This recurrent training is in addition to regular instrument proficiency checks as required every 12 months under CASR Part 61.
Occurrence summary
Investigation number
AO-2025-026
Occurrence date
05/06/2025
Occurrence time and timezone
1031 Australian Western Standard Time
Location
28 km west of Meekatharra Airport
State
Western Australia
Report release date
04/06/2026
Report status
Final
Investigation level
Defined
Investigation type
Occurrence Investigation
Investigation phase
Final report: Dissemination
Investigation status
Completed
Mode of transport
Aviation
Aviation occurrence category
Fuel starvation
Occurrence class
Incident
Highest injury level
None
Aircraft details
Manufacturer
Piper Aircraft Corp
Model
PA-31-350
Registration
VH-PGO
Serial number
31-7852109
Aircraft operator
Shine Aviation
Sector
Piston
Operation type
Part 135 Air transport operations - smaller aeroplanes
Activity
Commercial air transport-Non-scheduled-Passenger transport charters
On 26 November 2024, an instructor was conducting training operations with a student pilot in a Piper PA-28-180 Cherokee aircraft. Activities involved general aircraft handling in the Parafield Airport training area, South Australia, before returning to the aerodrome for circuit operations on runway 26L.
Around 1345 local time, as the aircraft was descending through about 600 ft on final approach to the runway, the student advanced the throttle to correct the descent profile when the engine did not respond. The instructor assumed aircraft control and began troubleshooting actions while managing the descent. At about 300 ft, when it was evident that the engine would not respond, the instructor committed to an emergency landing on the grassed area to the east of runway 21L. The landing was uneventful, and the student and instructor evacuated the aircraft without injury. The aircraft was undamaged.
Examination of the aircraft’s systems after the landing found that the fuel selector was in the left tank position – being the tank that was selected before the flight commenced. On inspection, the left tank contained no usable fuel.
Aircraft information
The Piper PA-28-180 aircraft has two independent fuel tanks within the wings, which feed the engine via a ‘Left-Right-Off’ selector valve located on the cockpit left side. The quantity of fuel in each tank is indicated by dash-mounted gauges. A fuel pressure gauge is co-located with the quantity gauges.
The aircraft manufacturer’s Pilot’s Operating Handbook (POH) lists the following actions in the event of a loss of engine power in-flight:
Fuel Selector – switch to another tank containing fuel
Electric Fuel Pump – On
Mixture – Rich
Carburettor Heat – On
Engine Gauges – check for an indication of the cause of Power Loss
Primer – Check Locked
If no fuel pressure is indicated, check tank selector position to be sure it is on a tank containing fuel.
Safety action
Following the occurrence, the operator’s Head of Operations reviewed the known details of the incident flight with all instructors, highlighting the absence of a ‘both tanks’ fuel selection on the PA-28 aircraft and reinforcing the requirement to use calculated fuel logs that are cross‑referenced against the aircraft gauges at periodic intervals during flight.
Safety message
All general aviation pilots must ensure they are fully familiar with the control and operation of the fuel system/s of the aircraft they are operating. This includes actions in the event of engine power loss at any phase of flight, where timely and appropriate responses to possible fuel flow interruptions can be critical to a safe outcome. Emergency checklists should be readily accessible and periodically reviewed to ensure pilots remain familiar with the appropriate actions in the event of fuel-related engine power loss.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Occurrence summary
Mode of transport
Aviation
Occurrence ID
AB-2024-047
Occurrence date
26/11/2024
Location
Parafield Airport
State
South Australia
Aviation occurrence category
Engine failure or malfunction, Forced/precautionary landing, Fuel starvation
Highest injury level
None
Brief release date
18/02/2025
Aircraft details
Manufacturer
Piper Aircraft Corp
Model
PA-28-180 Cherokee
Sector
Piston
Operation type
Part 141 Recreational, private and commercial pilot flight training
On 29 September 2024, at about 1225 local time, an Intermountain Manufacturing Co A-9A (A-9) was conducting glider towing operations at Lake Keepit aircraft landing area, New South Wales (NSW).
It was reported that, prior to the flight, the aircraft had a minor fuel leak on the left fuel tank drain port. Due to the leak, club policy was to only operate the left fuel tank on the ground, thereby minimising the potential fuel leakage from the left-wing tank.
Operations commenced at approximately 1030 local time and following the completion of the fourth tow and glider release at about 1224, the aircraft conducted a descent from the north-west of the landing area, intending to join a crosswind[1] for runway 20 (Figure 2).
During a slow left banked turn, on the northern side of the airfield at about 1,500 ft, the engine experienced a sudden loss of power. The pilot attempted to troubleshoot, however was unable to restore normal power to the engine.
The pilot made the decision to close the throttle and conduct a glide approach, broadcasting a PAN-PAN call with intentions to land on runway 14. The engine continued to operate at idle power during the subsequent descent and landing.
The aircraft landed without incident before clearing the runway and taxiing to a suitable parking area. The engine was reported to be operating normally at this time and a normal shutdown was conducted.
Figure 2: Approach path of aircraft
Source: Google earth, annotated by the ATSB
The operator reported that the loss of power in the engine was due to fuel starvation from an incorrect fuel tank selection. The left tank was being operated in flight, with the pilot believing that the fuel was being sourced from the right fuel tank.
The pilot reported having 233 hrs of total time of which 6.9 hrs were on type.
The fuel selector switch in the A-9 is non-traditional to that of some other conventional aircraft types, such asCessna, Piper, Beechcraft. In those aircraft, the handle is used to indicate the selector (for example, a Cessna 172 is shown in Figure 3, right). In comparison, in the A-9 (Figure 3, left), the fuel selector switch points to the selection so that the longer handle is placed on the opposite side of the tank to which the pilot wishes to select. (There are only left, right and 2 off positions for the selector.)
Figure 3: Fuel selector for the A-9 (left) and as a comparison, a Cessna 172 (right)
Source: Operator photos annotated by the ATSB
Safety message
Accidents involving fuel mismanagement are an ongoing aviation safety concern and pilots are reminded of the importance of understanding an aircraft’s fuel supply system and being familiar and proficient in its use.
Pilots should familiarise themselves with the Civil Aviation Safety Authority publication Advisory Circular AC 91-15v1.1 Guidelines for aircraft fuel requirements, which provides further guidance for in-flight fuel management.
Practising forced landings from different altitudes under safe conditions can help pilots prepare for an emergency situation, should one arise. Being familiar with emergency checklists and your aircraft’s systems will assist in an emergency when identifying and managing an engine failure.
Examples of other ATSB investigations covering starvation related occurrences include:
Fuel starvation and ditching involving Piper PA-28, VH-FEY, 15 km north-west of Jandakot Airport, Western Australia, on 20 April 2023 (AO-2023-021).
Fuel starvation event involving Cessna 310, VH-JQK, near Sunshine Coast Airport, Queensland, on 18 August 2022 (AO-2022-040).
Fuel starvation involving Cessna 206, 3.5 NM NE of Aldinga, South Australia, on 3 February 2019 (AB-2019-004).
Fuel starvation and forced landing involving Piper PA-28, VH-BDB, 15 km WSW of Bankstown Airport, New South Wales, on 19 September 2017 (AO-2017-094).
The 2013 ATSB publication AR-2011-112 details accidents involving fuel starvation due to fuel management. Ensuring a constant fuel supply to the engine/s during flight relies on the pilot’s knowledge of the aircraft’s fuel system and being familiar and proficient in its use, especially if the system is different to traditional aircraft.
About this report
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
[1]When arriving and intending to join the circuit from overhead, descend on the non-active side of the circuit so that the aircraft is established at its circuit altitude as it crosses the runway centreline on crosswind, between midfield and the departure end of the runway.
On 26 May 2024, a Cessna T210M, registered VH-MYW, was prepared for flight at Maitland Airport, New South Wales. The pilot planned to ferry the aircraft to Bankstown Airport, where the aircraft was to undergo maintenance. There was a pilot and one passenger on board.
During the approach, the engine stopped and while looking for a suitable landing place, the pilot saw a taxiway on the airport and decided to aim for that. To successfully reach the airport, the pilot elected to leave the flap retracted and gear up. This was done to reduce drag and achieve maximum glide range. Once the aircraft was assured of a landing on the airport, the gear was lowered. However, it did not successfully lock into place due to the limited time available before touchdown. The aircraft landed wheels-up resulting in minor damage and both occupants were uninjured.
What the ATSB found
The ATSB determined that, while the aircraft departed with sufficient fuel to complete the intended flight, it is likely that the amount of fuel reduced to a level that, in combination with unbalanced flight approaching Bankstown Airport, resulted in the engine being starved of fuel.
The ATSB also determined that the pilot's decision to carry non-essential crew placed the additional occupant at unnecessary risk of injury.
Safety message
Fuel starvation occurrences can often be prevented by conducting thorough pre-flight fuel quantity checks combined with inflight fuel management. Pilots are reminded to check fuel quantities prior to departure using a known calibrated instrument such as a dipstick. In addition, comparing the expected fuel burn with actual fuel remaining after a flight, will give a validated fuel burn for the aircraft and ensure the measuring equipment is accurate. Pilots should familiarise themselves with the Civil Aviation Safety Authority, Advisory Circular AC 91-15v1.1 Guidelines for aircraft fuel requirements, which provides further guidance for in‑flight fuel management.
Practising forced landings from different altitudes under safe conditions can help pilots prepare for an emergency situation, should one arise. Some components of the aircraft such as flap and gear, increase drag and reduce the glide range. Being familiar with emergency checklists and your aircraft’s systems will assist in an emergency when identifying and managing an engine failure.
The investigation
Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 26 May 2024, a Cessna T210M, registered VH-MYW, was prepared for flight at Maitland Airport, New South Wales (NSW). The pilot planned to ferry the aircraft to Bankstown Airport, where the aircraft was to undergo maintenance. As the pilot had not previously operated to Bankstown Airport, they elected to carry a passenger, who was also a helicopter pilot, to assist with navigation and radio communication.
At 1313 local time, with the left fuel tank selected for take-off, the aircraft departed from runway 23[1] and tracked south. The pilot reported that about 4 minutes into the flight (while passing abeam Cessnock) they selected the fuller right tank, which they thought would reduce workload when entering Bankstown airspace. The aircraft entered the Visual Flight Rules (VFR) route[2] between Brooklyn Bridge and Prospect Reservoir at 1336 at approximately 2,000 ft.
Figure 1: Sequence of events
The image shows the sequence of events leading up to and during the forced landing, it highlights relevant places and reference times. Source: OzRunways flight data overlay on Google Earth.
The aircraft arrived overhead Prospect Reservoir at 1346 (Figure 1) and the aerodrome controller (ADC) instructed VH-MYW to maintain 1,500 ft and join the downwind leg of the circuit for runway 29R. An approximate 25° angle of bank turn was conducted to track toward a downwind join for runway 29R.
At 1347, the pilot reported joining downwind for 29R and the ADC instructed them to maintain 1,500 ft and provided them with updated Automatic Terminal Information Service (ATIS) [3] information ‘Foxtrot’. The pilot confirmed receipt of the new information by reading back the new QNH.[4]
The pilot recalled that, at about the time of that radio transmission, with the aircraft about 4.5 km north-west of Bankstown Airport, the propeller RPM increased, and they felt a braking sensation. They recalled that, in response they attempted to reduce drag on the propeller, changed fuel tank selection and briefly selected the electric fuel boost pump to ON. They then aimed to maintain glide speed while looking for a place to land.
At 1348, the pilot transmitted a MAYDAY call on the Bankstown Tower radio frequency stating they were having engine problems. The ADC advised that all runways were available, and they could track as required. The ADC continued to coordinate traffic to assist VH-MYW.
The pilot reported that while they were looking for a place to conduct a forced landing, they saw a taxiway on the airport and decided to try to land there. They advised that, during the approach the aircraft clipped the top of a tree and they raised the aircraft’s nose at the last minute to avoid a building on the airport perimeter. They decided not to deploy landing gear or flap until they were assured of reaching the airport.
At 1350, a helicopter operating in the area, reported that the aircraft had landed at the intersection of taxiway November 1 and taxiway Lima.
Both occupants of the aircraft were uninjured, and the aircraft sustained minor damage.
Context
Pilot
The pilot held a private pilot licence (aeroplane) issued in 2014 with a single‑engine class rating. They were appropriately endorsed to fly the Cessna 210 with design features for manual propeller pitch control and retractable undercarriage. The pilot also held a current class 2 aviation medical certificate.
They had accrued a total flight experience of approximately 222 hours, of which 15 hours were on the Cessna 210. In addition, they had previously flown other aircraft in this range including the Cessna 206 and Cessna 177. The pilot’s licence showed an entry for a single‑engine flight review conducted on 31 May 2023.
Weather
At the time of the incident, the Automatic Terminal Information Service information ‘Foxtrot’ was current, which indicated CAVOK[5] conditions, temperature 22°C, wind direction variable at 5 kt, and runway 29R in use for arrival and departures.
Aircraft
The aircraft was a Cessna Aircraft Company T210M manufactured in 1978 and issued serial number 21062277. It was powered by a fuel‑injected Continental Motors Inc TSIO-520-R piston engine driving a 3‑bladed, constant‑speed McCauley Propeller.
The aircraft was purchased from South Africa where it was previously registered as ZS-MYV and was shipped to Australia where it was reassembled and placed on the Australian register on 19 March 2021 as VH-MYW.
Maintenance
The aircraft was issued a maintenance release in November 2022 for private operations however, this expired in November 2023. At the time of the incident the aircraft was being ferried to Bankstown for completion of the maintenance required to return the aircraft to service.
As the maintenance release had expired, a special flight permit (SFP) was issued for the purpose of completing this ferry flight. The SFP was issued by the Civil Aviation Safety Authority (CASA) on 14 May 2024. The permit expired on 31 May 2024 and was subject to the following conditions:
Essential operating crew only to be carried.
Daily inspection and flight times are to be recorded on the Maintenance Release.
Day VFR, non-commercial operation by the most direct route practical and permitted by weather.
Operation shall be conducted in accordance with the approved flight manual / cockpit placards for the aircraft.
A copy of this SFP to be carried on-board and filed with the aircraft logbooks.
The permit also stated the flight was permitted to depart Maitland and arrive at Bankstown.
The last daily inspection signed on the aircraft maintenance release was completed on 2 November. The pilot advised that they had completed the daily inspection prior to the flight, but this was not recorded on the maintenance release.
The aircraft maintenance release also carried 2 endorsements for defects. These included the wing flaps not extending equally and hail damage. The flap defect was addressed by a third party, however, the hail damage was assessed by the aircraft owner in accordance with the CASA Airworthiness Bulletin 51-010 Assessment of hail damage.
Airworthiness Bulletin 51-010 recommended having a person who was appropriately qualified under Civil Aviation Safety Regulations 21.M to inspect the aircraft.
The pilot reported the aircraft had a tendency to fly right wing down. There was insufficient evidence available to the ATSB to determine whether either of the aircraft defects contributed to the flight characteristics described by the pilot.
Aircraft systems
Trim
The aircraft was fitted with elevator and rudder trim. Rudder trimming was accomplished via a wheel mounted in the cockpit (Figure 2). Setting the rudder trim left of centre would result in the aircraft maintaining the nose left of the flight path and remaining in that position until the wheel was manipulated, or the rudder pedals were manipulated. To maintain the desired track with that trim configuration, the aircraft would need to be flown in an uncoordinated state with the right wing low.
The aircraft’s pilot operating handbook stated:
Unusable fuel is at a minimum due to the design of the fuel system. However, when the fuel tanks are ¼ full or less, prolonged uncoordinated flight[6] such as slips or skids can uncover the fuel tank outlets, causing fuel starvation and engine stoppage. Therefore, with low fuel reserves, do not allow the airplane to remain in uncoordinated flight for periods in excess of one minute.
Cessna advised this was originally added to the Cessna 210 model D owner’s manual and was carried through as the aircraft developed into different models. Cessna did not have the available data to assess the likelihood of uncoordinated flight contributing to fuel starvation.
The pilot stated the rudder trim had been set left of centre since the aircraft was re‑assembled in Australia and that the trim wheel was not manipulated in flight.
Figure 2: Aircraft control pedestal post-incident
The image shows the fuel gauge level and the rudder trim. The image was taken on 6 June 2024, several days after the incident. However, the person responsible for recovering the aircraft stated, no fuel was added prior to this photo and the trim was set as found on the day of the incident. Source: Engineer responsible for aircraft recovery.
Fuel system
The Cessna 210 fuel system consists of a main fuel tank located in each wing. Each tank capacity is 171 L, of which 169 L is usable fuel. Each tank gravity fed a smaller fuel reservoir tank of approximately 1.9 L through fuel collector ports, which were located at the forward and aft inboard side of the main fuel tank (Figure 3Figure 3 and Figure 4).
Figure 3: Cessna 210M fuel schematic
Source: Cessna 210M pilot operating handbook, annotated by the ATSB
The fuel selector valve had 3 positions – left, right, and off – and so fuel could only be drawn from either the left or right tank. Cessna advised that at a low cruise power setting, if no fuel was being fed to the smaller fuel reservoir tank, it could supply fuel to the engine for between 1.5–3.5 minutes. The pilot advised that, at the time of the power loss the fuel selector was selected to the right fuel tank.
The fuel system has an engine-driven fuel pump and an auxiliary fuel pump, which is electrically driven. The pilot operating handbook states the following:
If it is desired to completely exhaust a fuel tank quantity in flight, the auxiliary fuel pump will be needed to assist in restarting the engine when fuel exhaustion occurs.
Cessna stated that during testing, the electric auxiliary fuel pump was required to operate for 4 seconds to restart the engine.
Figure 4: Fuel tank design
The above image shows the location of the fuel collector ports and the openings that are located in the rib support structure. The fuel cell image shown is for later serial numbers of the Cessna 210. However, it is the most descriptive image of fuel collector ports. Further images provided by Cessna show the aft collector port is located in a similar location to the above image. Source: Cessna 210 illustrated parts catalogue model 210 & T210 series 1981–1986, annotated by the ATSB.
The fuel tank design included an internal rib support structure (Figure 4). Each rib had an enlarged centre opening for fuel to freely flow through the tank, with small openings at the base of each rib, ensuring useable fuel could not become trapped. Cessna stated, ‘The small, if any, amount of fuel caught behind any structure would be part of the unusable fuel level determined during certification.’
Propeller
A control lever was used to set aircraft RPM by changing the propeller blade pitch. When the control lever is pushed inward, the propeller increases RPM (low blade pitch). When the control lever is pulled outward, the propeller RPM decreases (high blade pitch). This is achieved by a propeller governor which relies on engine oil pressure to move the propeller toward a high blade pitch (low RPM).
The combination of an internal spring and centrifugal force, twists the blades toward a low pitch (high RPM) setting when oil pressure at the propeller hub is relieved.
Engine Failure During Flight checklist
The pilot operating handbook provided the following checklist to be conducted in the event of an engine failure during flight:
airspeed – 85 [kt indicated airspeed] KIAS
fuel quantity – check
fuel selector valve – fuller tank
mixture – rich
auxiliary fuel pump – on for 3-5 seconds with throttle ½ open; then off
ignition switch – both (or start if propeller is stopped)
throttle advance slowly.
Flight data
The ATSB obtained flight data from an electronic flight bag (EFB) used by the pilot. The data provided aircraft position, time, altitude, and ground speed.
The flight data was analysed by the ATSB to obtain the approximate position when the engine stoppage occurred. This was determined to be at 1348 as there was a significant reduction in ground speed at that time.
Flight planning and fuel usage
The pilot reported that during the cruise, the manifold pressure was set near the top of the green (approximately 25 inches) and RPM at 2,200. A fuel flow reading was noted by the pilot of 14 gallons per hour (53 L/hr).
The pilot advised that they normally dipped the tank during the pre-flight inspection using the aircraft’s fuel dipstick. During the pre-flight they estimated 150 L of fuel on board, 60 L in the left tank and 90 L in the right tank (see the section titled Fuel system). Using that fuel quantity and recorded flight data, Table 1 details the expected consumption throughout the flight.
Table 1: Estimated fuel burn based on flight data
Sector
Start time
Block time
(min)
Estimated fuel burn (L) at 53 L/hr
Total
Comments
Departing Maitland
1313
0
5
145
Pilot stated, they departed on left tank (5 L allowed for taxi)
Abeam Cessnock
1317
4
4
141
Climbing phase, fuel burn was likely higher than 53 L/hr.
Near Warnervale
1325
8
8
133
Pilot stated, at approximately overhead Cessnock, they swapped to right fuller tank.
Brooklyn Bridge
1336
11
10
123
Prospect Reservoir
1346
10
9
114
Estimated engine stop
1348
2
2
113
Total
35
38
Totals have been rounded up
Post-incident inspection
The ATSB did not attend the site. A video of the aircraft, provided by 9News Australia showed fuel leaking from the right fuel tank vent. The aerodrome operator who attended the incident site stated that the fuel which leaked from the vent was no more than 2–4 litres, of which most was funnelled into a jerrycan. While the ATSB could not verify how long the fuel was leaking, based on the observations of the aerodrome operator, it was unlikely to have significantly affected the amount of fuel in the tank. There was no evidence of fuel leaking from the left tank.
Figure 5: Fuel leak from right tank vent
Source: 9News Australia
The aircraft was recovered, and an initial inspection was completed. The fuel level was checked using the on-board fuel gauges and dipstick. The left tank was estimated to hold between 0–5 L and the right tank was estimated between 40–50 L.
The aircraft’s damaged propeller was removed, and a suitable test propeller was fitted to the aircraft. The engine was started and was able to draw fuel from the remaining fuel in both tanks, the test continued for approximately 5 minutes on each tank. However, high power settings similar to in‑flight conditions were not tested.
The aircraft had undergone a fuel calibration and the placard above the fuel gauges was no longer relevant however, it was not removed (Figure 2). The placard was not considered to have contributed to the incident as the fuel on board was likely less than the 4 hours stated on the placard. The onboard fuel dipstick used was labelled C210 dipstick and was marked with the aircraft’s previous registration, ZS-MYV.
Related occurrences
Fuel management and fuel starvation incidents and accidents continue to occur with single and twin-engine aircraft. Examples of other ATSB investigations of similar occurrences include:
Fuel starvation and forced landing involving Piper PA-31-350, VH-HJE, 11 km south of Archerfield Airport, Queensland, on 7 April 2023 (AO-2023-017)
Fuel starvation and ditching involving Piper PA-28, VH-FEY, 15 km north-west of Jandakot Airport, Western Australia, on 20 April 2023 (AO-2023-021)
Fuel starvation and forced landing involving Pilatus Britten-Norman Islander BN2A, VH-WQA, Moa Island, Queensland, on 3 October 2022 (AO-2022-046).
Safety analysis
The pilot reported that, during approach to Bankstown Airport, they noted an increase in propeller RPM and could not maintain altitude. This behaviour was consistent with an engine failure, with the associated loss of oil pressure resulting in the propeller moving to a finer pitch (increased RPM). The post-incident aircraft inspection did not identify an engine malfunction, and the engine was able to run at low power on the remaining fuel in both tanks. As there was no evident malfunction of the engine, the most probable reason for the inflight power loss was fuel starvation.
The pilot reported that the aircraft departed with 90 L in the right tank and 60 L in the left tank (150 L total). They also advised the right tank was selected for most of the flight. If this was the case, there should have been approximately 61 L in the right tank and 51 L in the left tank. However, given the total fuel on board after the incident occurred (maximum 59 L), it was unlikely that approximately 91 L was burnt during the 35-minute flight. Therefore, it was unlikely that the amount of fuel the pilot stated was on board at the commencement of the flight was actually in the aircraft. Significantly however, there was sufficient total fuel on board for the flight.
The post-incident inspection revealed between 40–50 L remaining (which equated to approximately 1/4 full tank) in the right tank, with about 2–4 L reportedly leaking after the landing. The pilot operating handbook (POH) stated that if there was less than 1/4 fuel in the tank and the aircraft was in uncoordinated flight, the fuel pick-ups could uncover, and fuel starvation could occur.
The post-incident inspection also revealed between 0–5 L remaining in the left fuel tank. If the engine was being supplied from the left tank, during an uncoordinated left turn at Prospect Reservoir at 1346, it is possible the fuel drained away from the fuel pick-ups and the engine continued to draw fuel from the left header tank until 1348 when the engine stopped. This was consistent with Cessna’s advice that the header tank can supply fuel for 1.5–3.5 minutes at low cruise power.
In summary, irrespective of which tank was supplying the engine, the quantities of fuel remaining, when combined with the uncoordinated flight, were conducive to fuel starvation in accordance with the POH.
The pilot’s initial response during the emergency was largely focused on attempting to reduce drag created by the propeller, despite the aircraft not having this ability, and they did not complete the engine failure during flight checklist. If the checklist had been followed, the pilot would have increased the likelihood of restarting the engine in flight. During the extended period where the aircraft was resting on the ground and positioned right-wing low, it is likely the fuel remaining in the left tank drained into the left header tank. Even though this fuel was sufficient to run the engine at low power, it may not have been available during approach or sufficient for the power required in flight.
The pilot’s decision to minimise the aircraft’s drag during the glide, by keeping the gear up and flaps retracted, combined with managing the airspeed, resulted in the aircraft achieving the required performance to land safely inside the airport environment. However, due to the distance the aircraft needed to glide and obstacles that needed to be cleared, by the time the landing gear was selected down, there was not enough time to extend and lock in place before the aircraft collided with the ground resulting in a wheels-up landing.
Finally, the CASA special flight permit was issued for the purpose of ferrying the aircraft for maintenance. The conditions put in place were to minimise the consequences if an incident occurred during flight which was conducted outside of the normal aircraft operation. Although their reported purpose was to assist with navigation and radio communication, the pilot’s decision to allow a passenger to fly on board the aircraft unnecessarily exposed them to a risk of injury and consequently was another factor that increased risk.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the fuel starvation involving Cessna T210M, VH-MYW, 4 km north-west of Bankstown Airport, New South Wales, on 26 May 2024.
Contributing factors
While the aircraft departed with sufficient fuel to complete the intended flight, low usable fuel quantities, in combination with probable uncoordinated flight approaching Bankstown Airport, resulted in the engine being starved of fuel.
Other factors that increased risk
The pilot's decision to carry non-essential crew placed the additional occupant at unnecessary risk of injury.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot
aerodrome operator
engineer responsible for aircraft recovery
aircraft manufacturer and insurer
Civil Aviation Safety Authority
Airservices Australia
OzRunways recorded data
video footage of the incident flight and other imagery taken on the day of the incident.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
pilot
engineer responsible for aircraft recovery
Civil Aviation Safety Authority
aircraft manufacturer.
Submissions were received from the:
pilot
Civil Aviation Safety Authority.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1]Runway number: the number represents the magnetic heading of the runway. The runway identification may include L, R or C as required for left, right or centre.
[2]VFR route: A pre-defined laneway for aircraft traffic to remain clear of airspace and enter or exit high traffic areas such as Bankstown Airport.
[3]Automatic terminal information service: The provision of current, routine information to arriving and departing aircraft by means of continuous and repetitive broadcasts. ATIS information is prefixed with a unique letter identifier and is updated either routinely or when there is a significant change to weather and/or operations. See Automatic terminal information service (ATIS).
[4]QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean seal level.
[5]Ceiling and visibility okay (CAVOK): visibility, cloud and present weather are better than prescribed conditions. For an aerodrome weather report, those conditions are visibility 10 km or more, no significant cloud below 5,000 ft, no cumulonimbus cloud and no other significant weather.
[6]Uncoordinated flight occurs when the aircraft skids or slips, this is most commonly associated with a turn, but a skid can occur when the ailerons and rudder are used in opposite directions during normal flight.
Occurrence summary
Investigation number
AO-2024-033
Occurrence date
26/05/2024
Location
4 km north-west of Bankstown Airport
State
New South Wales
Report release date
11/10/2024
Report status
Final
Investigation level
Short
Investigation type
Occurrence Investigation
Investigation status
Completed
Mode of transport
Aviation
Aviation occurrence category
Collision with terrain, Engine failure or malfunction, Forced/precautionary landing, Fuel starvation, Wheels up landing
Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified.
What happened
On 8 March 2024, at about 1304 local time, the pilot of a Beech Super King Air 200 departed King Island Airport, Tasmania, on a private ferry return flight to Moorabbin Airport, Victoria. The pilot was the only person on board.
Passing FL160[1] on climb, the left fuel pressure and left oil pressure warning lights illuminated, and the left engine stopped shortly after. The pilot levelled off and conducted initial actions for an engine failure, secured the left engine and advised air traffic control of the engine failure. Due to the unknown fuel state onboard, the pilot conducted a return to King Island.
On descent, the pilot began to troubleshoot and identified that the engine failure was due to fuel starvation and cross-fed fuel from the right fuel system to the left engine nacelle tank, and successfully restarted the left engine. The pilot reported only using low power settings for the left engine due to concern that there would be insufficient fuel for a go-around if a higher power setting was used. The pilot conducted a normal visual approach and landing at King Island. Upon landing, the pilot checked the fuel quantity and confirmed the fuel reserves were intact.
Fuelling history
The pilot received a late roster change the previous evening which prevented them from ordering fuel for the next day. This resulted in the pilot using a company bowser in the morning which did not contain enough fuel for the planned flying that day. The pilot planned to use the remaining 700 litres of fuel in the bowser to add 350 litres to each wing. However, due to a higher than expected fill rate from the bowser, 450 litres was inadvertently added to the right fuel tanks leaving only 250 litres to add to the left fuel tanks. This resulted in a difference of 200 litres between the left and right tanks, which was within the permitted fuel discrepancy published in the pilot operating handbook. When refuelling later in the day, the pilot added 150 litres of fuel per side, however, did not correct the fuel imbalance of 200 litres.
During the flight from Moorabbin to King Island prior to the occurrence flight, the pilot detected an issue with the left fuel gauge which displayed erroneous figures. An MEL[2] was applied for the unserviceable gauge with the use of right fuel gauge only for the return sector to Moorabbin. The pilot made the decision to rely on mirroring the right fuel gauge for flight planning and inflight fuel calculations, omitting the 200 litre fuel difference.
Beech Super King Air 200 fuel system
The Super King Air 200 fuel system comprises two separate systems (one in each wing) connected by a valve-controlled cross-feed line. Within each fuel system, fuel is automatically transferred from the main and auxiliary tanks into a collector nacelle tank located directly behind the engine. In the event that one of the fuel systems is empty, fuel can be cross-fed directly to the engine from the nacelle tank in the opposite wing’s fuel system.
Safety message
Fuel starvation occurs when the fuel supply to the engine(s) is interrupted although there is usable fuel on board.
This incident reinforces the need to:
verify pre-flight fuel quantity to determine usable fuel available
use a fuel log during flight to provide a record of fuel consumption from each tank and assess remaining fuel on board when refuelling
be fully familiar with the fuel system’s operation.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
[1]FL – Flight level: at altitudes above 10,000 ft in Australia, an aircraft’s height above mean sea level is referred to as a flight level (FL). FL370 equates to 37,000 ft.