Collision with terrain

Landing gear malfunction and collision with water involving de Havilland Aircraft of Canada DHC-2 Beaver, VH-OHU, near Whitehaven Beach, Whitsunday Island, Queensland, on 26 October 2024

Final report

Report release date: 10/11/2025

Investigation summary

What happened

On the morning of 26 October 2024, the pilot of a De Havilland Aircraft of Canada DHC‑2 Beaver aircraft, registered VH‑OHU, departed Hamilton Island aerodrome, Queensland, with 4 passengers on board, for a 10-minute scenic flight to Whitehaven Beach, Whitsunday Island. The aircraft touched down on the water with the right main gear not retracted into the float. As a result, the aircraft rapidly yawed to the right, nosed over and became submerged inverted. The pilot self-evacuated and then, when they found no one else on the water surface, promptly returned to help the passengers egress. The pilot and 4 passengers sustained minor injuries, and the aircraft was substantially damaged.

What the ATSB found

The ATSB found that, after departing Hamilton Island, the right main landing gear did not retract and had seized in the extended position, likely due to corrosion. For undetermined reasons, the pilot did not identify that the right main gear had remained extended during their pre-landing checks, either via the landing gear position indication panel, the amphibian gear advisory system (AGAS) annunciation or the wing-mounted mirror. 

In addition, the ATSB noted that the AGAS annunciation alert for an asymmetric configuration, which required immediate pilot action, was similar to a normal gear position advisory. This increased the risk that a pilot would not recognise that the gear was in an unsafe condition for a water landing.

Following the collision with water, and with the aircraft submerged and inverted, the left rear cabin door could not be opened by the pilot or passengers, which delayed their egress. However, the pilot opened the right main door and assisted all passengers to evacuate.

As required by the operator, the pilot had completed helicopter underwater escape training about one month prior to the accident and credited this as a life-saving course.  

Following several floatplane accidents in Canada, the Transportation Safety Board of Canada recommended the fitment of regular and emergency exits that allowed rapid occupant egress following a survivable collision with the water. Viking Air Limited subsequently developed push-out windows and revised more intuitive automotive-style door latches for the rear cabin door on the DHC‑2 aircraft. These modifications were not fitted to VH-OHU nor were they required by regulations. 

What has been done as a result

In response to the accident, Hamilton Island Air advised it has implemented formal initial and refresher training for pilot maintenance tasks, as well as installation of a second mirror on the right wing of its current DHC‑2 aircraft. It has developed a sign-off form to document the daily washdown and preventative maintenance procedures. In addition, it incorporated a minimum weekly systems check flight, including landing gear cycle, where the aircraft had not been recently operated. Further, it introduced annual theory training and 180-day proficiency flight checks, conducted by authorised flight training organisations.

The Civil Aviation Safety Authority has developed airworthiness bulletin AWB 32-029 Issue 1 Supplementary Type Certificated Amphibian Float Main Gear Slide Wear in Marine Environments. The bulletin recommended enhanced vigilance and maintenance actions on the landing gear components to ensure reliability of the landing gear and the actuating system.

Safety message

As shown in this accident, inadvertent water landings in amphibian aircraft with one or more gear extended can rapidly result in the aircraft becoming submerged and inverted. This investigation reinforces the effectiveness of helicopter underwater escape training, not exclusively for helicopter pilots but also for pilots who operate any type of aircraft over water such as floatplanes.

Further, this accident highlights the value of having alternate means of exiting an aircraft post-accident. This is particularly important if the pilot is unable to assist and/or the fuselage is distorted, to increase the occupants’ chance of survival in the event of an impact with water.

Safety Watch logo

The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. One of the safety concerns is reducing the severity of injuries in accidents involving small aircraft.


The investigation

The ATSB scopes its investigations based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, the ATSB conducted a limited-scope investigation in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On the morning of 26 October 2024, a De Havilland Aircraft of Canada DHC‑2 Beaver amphibian floatplane, registered VH‑OHU and operated by Whitsunday Air Services (trading as Hamilton Island Air), was being prepared for a scenic flight from Hamilton Island to Whitehaven Beach (Whitehaven), Whitsunday Island, Queensland. The flight would typically be about 10–15 minutes, with about 75 minutes at Whitehaven, before returning to Hamilton Island.

Prior to boarding the aircraft, the 4 passengers viewed a pre-flight safety briefing video and were fitted with a pouch‑style constant wear lifejacket.[1] The pilot then conducted an additional briefing at the rear left cabin door of the aircraft. The passengers recalled this included being demonstrated how to use their seatbelts, don the lifejackets and operate the rear door handle, among other things. The passengers were seated, in pairs, in the middle and rear seat rows, with the seat to the right of the pilot not utilised.

The aircraft departed to the south-east and made a left turn to track toward Chance Bay, Whitsunday Island (Figure 1). The pilot reported that, during initial climb, they set climb power and selected the landing gear to retract (see Landing gear actuation system). The pilot noted the gear was cycling, as evidenced by the illuminated red ‘hydraulic pump’ lamps.  

At about Chance Bay, the pilot spoke with the pilot of a company helicopter that was following, via very high frequency radio transmission, to coordinate with them as they were both heading toward Tongue Point. From this location, the pilot observed the water conditions and location of boats moored along Whitehaven. They described their observation as 7 kt, from the south-east and about 3 or 4 vessels on the water at Whitehaven. They then reported observing 4 blue ‘gear up’ lights on the landing gear panel and they did not see any of the main wheels extended in the mirror mounted on the left wing (see Mirror). The pilot then conducted an orbit over Tongue Point and Hill Inlet, before making a turn and doing a second pass so all passengers could view the beaches and inlets below.

After advising the passengers they would shortly be landing, the pilot commenced the pre-landing cockpit flow checks, including isolating the passengers from the aircraft audio system. The pilot advised they confirmed 4 blue lights, ‘saw no gear visible out the left window’, completed their flow checks and commenced the descent for landing. The pilot broadcast their intent to land at the south end of Whitehaven. They then completed the ‘finals checks’ from memory, which included checking the landing gear position again, before focusing on the landing.

Figure 1: Whitehaven Beach with reference to Hamilton Island, with approximate flight path depicted in yellow
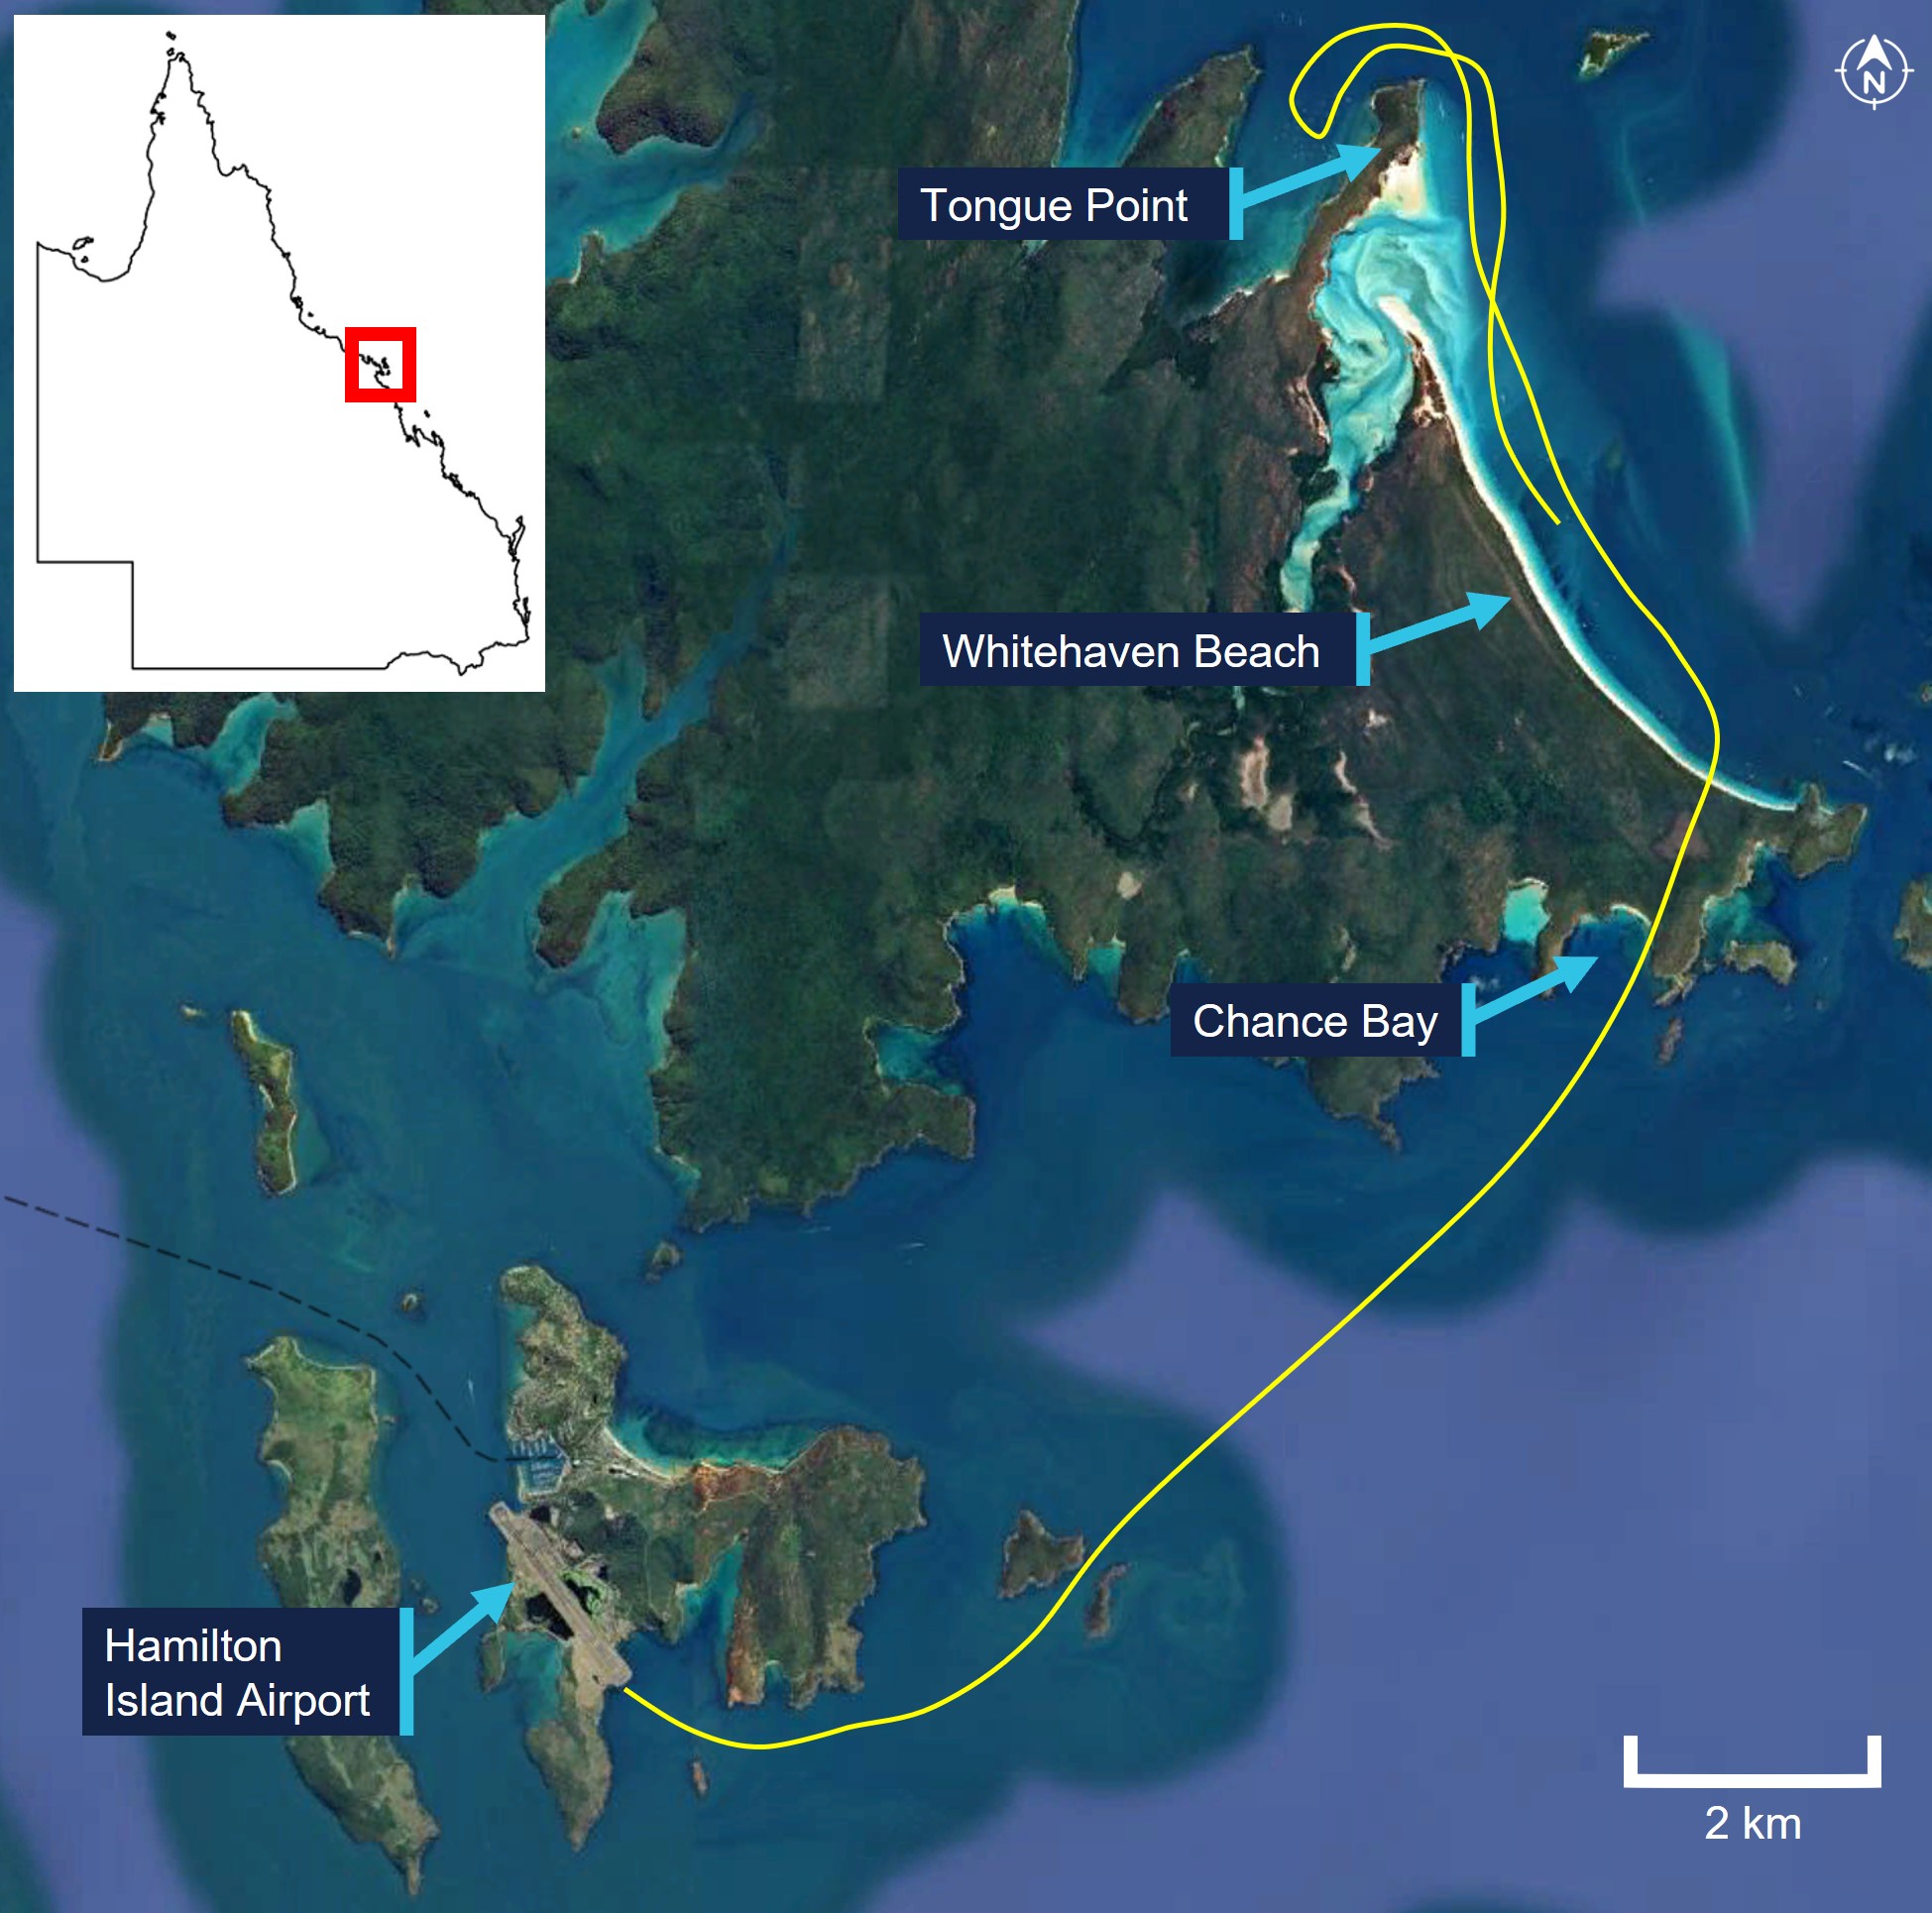
Approximate flight path drawn over map showing Hamilton Island and Whitehaven Beach

Note: Approximate flight path derived from limited passenger images and video footage. Source: Google Earth, annotated by the ATSB

Upon touching down on the water, the aircraft bounced, then yawed sharply to the right, before nosing over and becoming submerged inverted. With the aircraft quickly filling with water, the pilot released their seatbelt and went to open their door, which they reported required some force. On exiting the aircraft, their leg was caught in the seatbelt, however, they were able to free themselves and swam to the surface. At the same time, 2 of the passengers had released their seatbelts and were both trying to open the left rear cabin door, which was adjacent to where they had both been sitting. They turned the door handle one way, and tried the other way, but could not open the door.

When the pilot did not see any of the passengers on the water surface, they returned to the aircraft to help them. They swam down and attempted to open the rear left door. Despite considerable effort, with their feet positioned on the airframe either side of the door, the door would not open, so they swam over to the right rear cabin door. The right door was able to be opened, again with a degree of force required, and the pilot pulled the nearest person out and took them to the surface. After taking a breath, the pilot returned and retrieved a second person, before assisting the remaining passengers.

One of the passengers, when they realised they could not open the left rear door, and with the cabin now almost completely filled with water, swam to the right side of the aircraft. They saw their partner was still in their seatbelt, so released it and continued to search for the door handle. They then felt their partner being pulled from them and out of the aircraft. They do not recall how they exited the aircraft but found themselves on the surface. The other passenger who was initially attempting to open the left rear door reported observing their partner, but it was very difficult to see. They then recalled being pulled from the aircraft, however, their partner could not remember how they exited the aircraft.

A nearby vessel rendered assistance to the pilot and passengers and transported them to Hamilton Island for medical attention. Once aboard the vessel, the pilot looked at the aircraft and observed the right main gear wheels had not retracted into the float (Figure 2).

Figure 2: VH-OHU underside of floats, showing right main wheels not retracted

Image of overturned aircraft, post-accident, showing left main gear retracted into the float and right main gear extended.

Source: Used with permission, annotated by the ATSB

The pilot and passengers sustained minor injuries, and the aircraft was substantially damaged. It was reported that the aircraft sustained further damage during the retrieval from the water, before being transported to Mackay Airport, for storage.

Context

Pilot information

The pilot held a Commercial Pilot Licence (Aeroplane), with single and multi-engine class ratings and design feature endorsements including retractable undercarriage and floatplane. The pilot also held a current class 1 medical certificate with nil restrictions.

Prior to commencement with Whitsunday Air Services (trading as Hamilton Island Air), the pilot had accrued 563 hours total aeronautical experience, with 696 water landings, in a Cessna 182 aircraft on fixed floats. On 3 September 2024, the pilot underwent a familiarisation/transition flight in a fixed float DHC‑2 aircraft with an approved flight training organisation. The pilot was then employed with Hamilton Island Air. On 10 September 2024, the pilot commenced line training through the operator’s in‑command-under-supervision (ICUS) program, operating the DHC‑2 and the GippsAero GA8 Airvan[2] aircraft under the supervision of the operator’s ‘fixed wing specialist’ training pilot (see Operational information).

The pilot completed ICUS training with a line check on 8 October 2024. The training pilot set a 20 kt wind limitation for operations at Whitehaven for the next 25 flight hours, for the pilot to fine‑tune their skills ‘in the air and on the water’. The aircraft daily flight records indicated the pilot conducted solo flights on 15 and 25 October, consisting of circuit training at Hamilton Island. In addition, on 18 October they conducted a flight to Whitehaven, with 5 Hamilton Island Air staff as passengers, similar to the tour that was the accident flight. The accident flight was the pilot’s first flight with fare-paying passengers. 

As of the morning of 26 October, the pilot had accrued 28 hours and 84 water landings in VH‑OHU. While the pilot had accrued 84 water landings in an amphibian aircraft, typically, the landing gear was not required to be extended and then retracted during training that consisted of multiple water landings in one session. As such, their gear actuation cycle experience was likely lower.

Helicopter underwater escape training (see Helicopter underwater escape training) was a Hamilton Island Air requirement, for all its helicopter and fixed-wing flight crew, to be completed during their induction and followed by recurrent training every 2–3 years. The pilot completed their initial underwater escape training on 24 September 2024.

The pilot self-reported to being well rested and feeling ‘fully alert’ on the morning of 26 October 2024. In addition, they advised they ‘felt comfortable with the aircraft’ and they had no distractions during the preparations for landing at Whitehaven.

Aircraft information

General

VH‑OHU was an amphibian De Havilland of Canada DHC‑2 Beaver, serial number 826, a predominantly all metal high-wing aircraft manufactured in 1956 and first registered in Australia in 2015.

The DHC‑2 was originally designed and manufactured by De Havilland Aircraft of Canada, Limited. Viking Air Limited was the type certificate holder from 2006 until 2024. In August 2024, Viking Air Limited amalgamated with De Havilland Aircraft of Canada Limited, and De Havilland Aircraft of Canada Limited became the type certificate holder.

The aircraft was powered by a Pratt & Whitney ‘Wasp Junior’ R-985 9-cylinder, single row, air‑cooled radial engine, which drove a Hartzell HC B3R30-4B 3‑blade propeller. The aircraft was fitted with Wipline 6100 series amphibious floats, manufactured by Wipaire.

Cockpit and cabin configuration

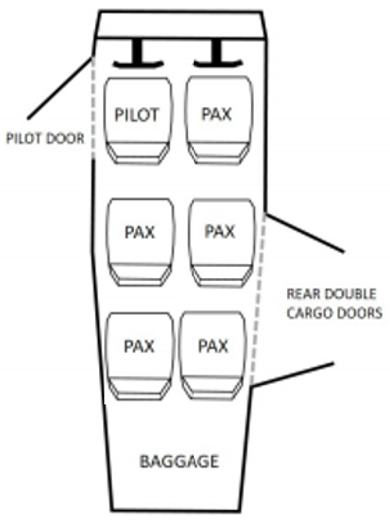
There were 2 forward cockpit doors and 2 rear cabin doors. The cabin door handle was located along the aft edge of the door and required the row 1 passenger to reach behind the seat to open the door (Figure 3). The front seats were equipped with 3-point lap-sash style restraints and the 3-person cabin bench seats were equipped with 2-point lap-belt restraints.

Figure 3: Seat and door locations
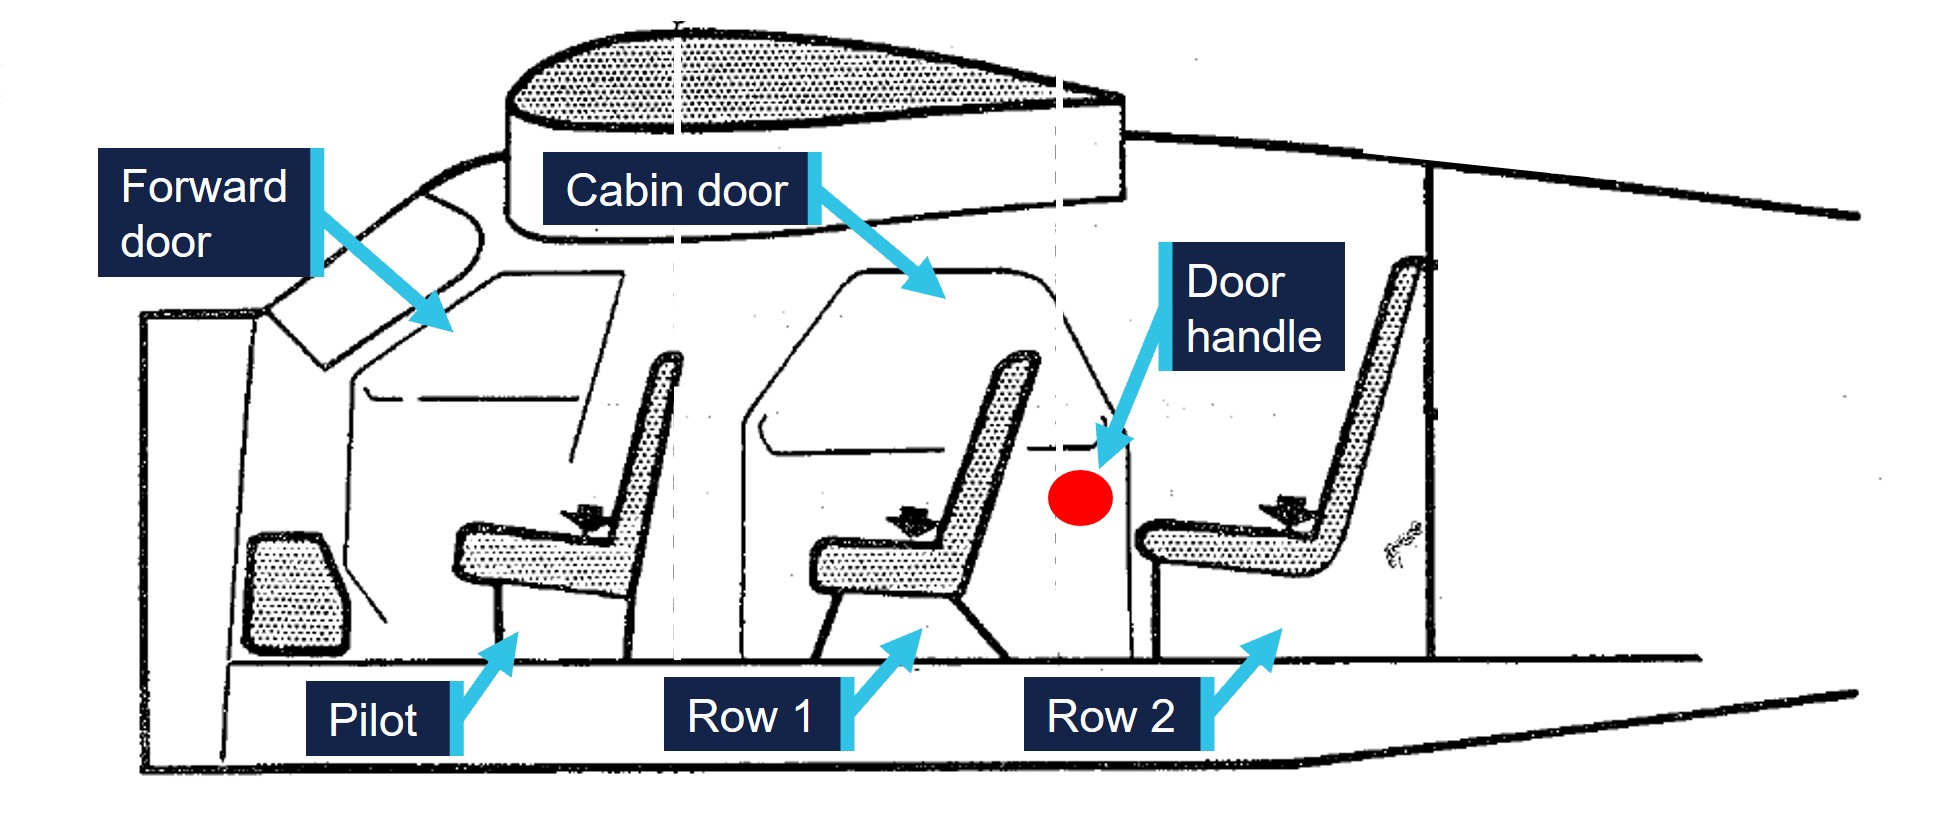
Diagram of DHC-2 cabin showing seat and door locations.

Source: Pilot’s operating handbook, annotated by the ATSB

Maintenance history

The aircraft logbook statement showed the airframe, electrical, engine, instruments and radio were to be maintained in accordance with the Civil Aviation Safety Authority (CASA) Schedule 5.[3] The float system was to be maintained in accordance with Wipaire instructions for continued airworthiness.

On 6 December 2022, VH‑OHU was subject to a forced landing just after take-off from Hamilton Island. The aircraft was subsequently removed from service. The aircraft was partly disassembled and transferred to Mackay in July 2023. Between January and September 2024, the aircraft underwent scheduled maintenance conducted by a CASA‑authorised maintenance organisation. Additional maintenance included treatment of corrosion and replacement of corroded hardware and components. This included inspection of the landing gear carriage assemblies and replacement of both slide tubes and all proximity sensor switches (see Landing gear actuation system). A landing gear system retraction test was also performed at this time.

The current maintenance release was issued on 3 September 2024 and there were no recorded defects at the time of the accident. The aircraft had accrued about 18 hours on the maintenance release, with a total time of 18,342 hours. Landings were recorded on the maintenance release, however, there was no distinction between water or land, nor if the gear had been retracted during water landing training or circuits from Hamilton Island.

Landing gear system
General

The landing gear incorporated within the amphibious floats is a retractable, quadricycle type with 2 free castoring nose (or bow) wheels and 4 (2 sets of dual) main wheels (Figure 4). Steering on the water is accomplished by a water rudder located at the rear of each float, which is cabled into the existing aircraft rudder system. Steering on land is accomplished by differential braking on the main landing gear wheels.

Figure 4: VH-OHU showing the amphibious float components
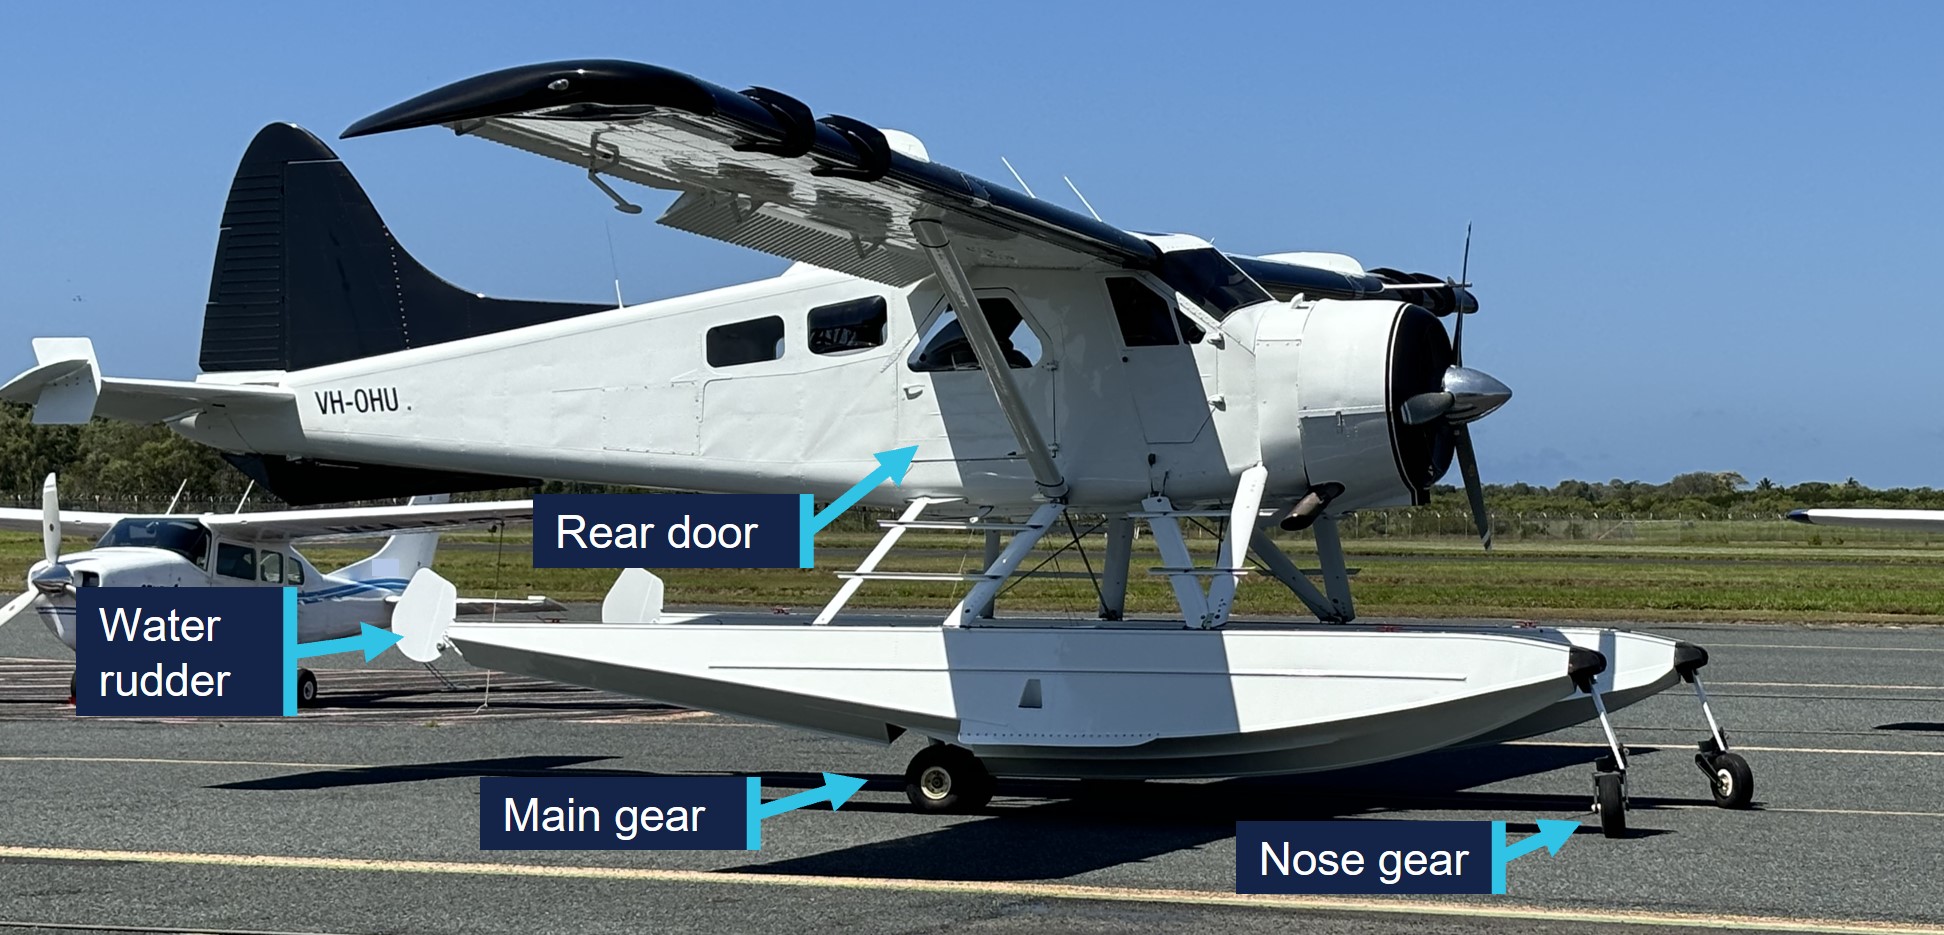
VH-OHU parked at an airport, showing amphibious float and landing gear components.

Source: Maintainer, annotated by the ATSB

Landing gear actuation system

Landing gear operation is initiated by movement of the landing gear handle, with the extension and retraction accomplished by 2 electrically‑driven hydraulic pumps. When the pilot selects the gear handle to UP or DOWN, hydraulic pressure in the system will drop and pressure switches will automatically turn on the hydraulic pump motors to maintain operating pressure in the system. When the gear cycle is completed, pressure in the system will increase to the limit where the pressure switches automatically shut off the pumps. If the pressure in the system drops to a preset value, the pressure switches turn the pump motors back on and build up the pressure to the limit again. Only the main gear system operation will be detailed in this report. 

The main gear is mechanically locked in both up and down positions. When the gear is selected to UP, the main gear down hook unlatches from the rear locking pin. Hydraulic pressure exerted on the actuator piston drives the carriage assembly to move forward along the slide tube, with the wheels moving aft, until the gear up hook latches on the forward locking pin (Figure 5). With no further movement once all 4 gear are retracted into the float, hydraulic pressure will increase until the pumps automatically switch off. 

Figure 5: Main gear assembly diagrams, including VH‑OHU forward locking pin (inset)
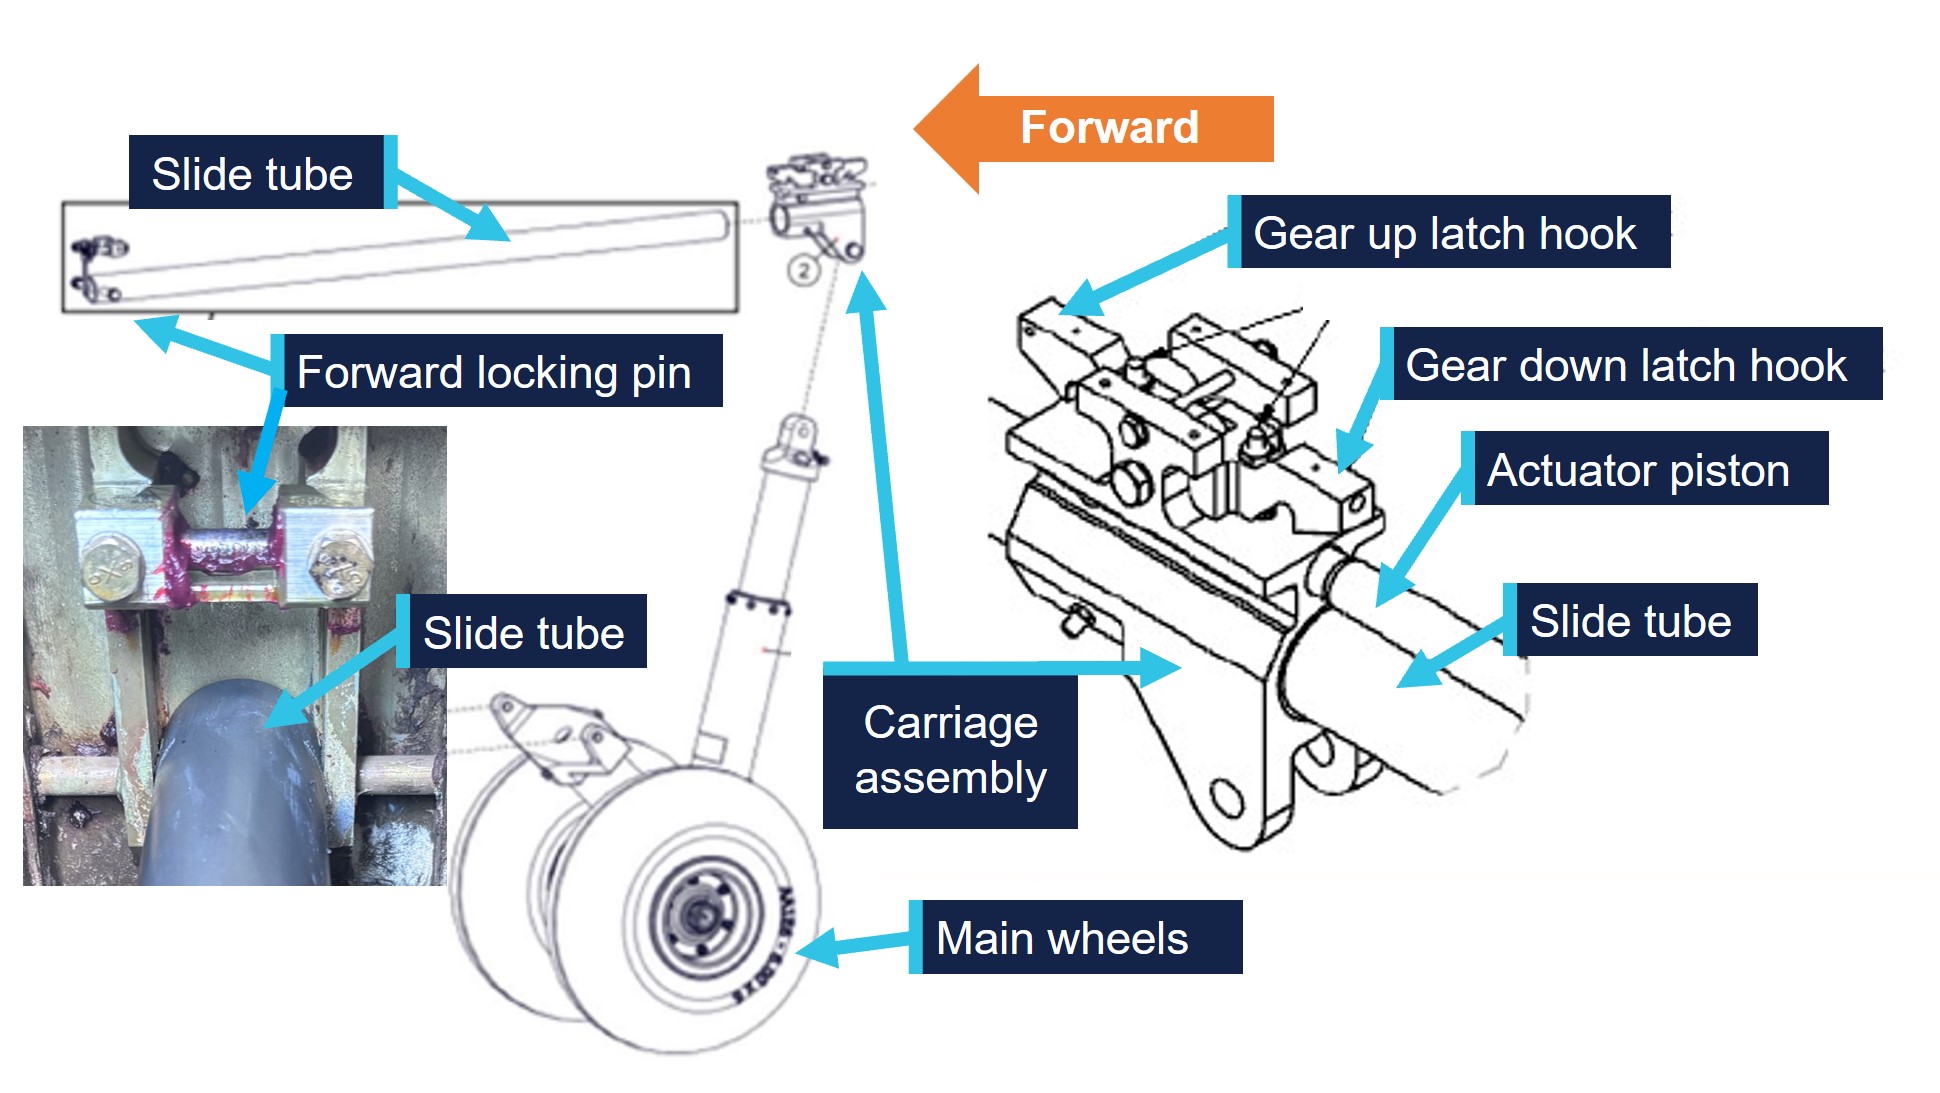
Drawing of main gear assembly showing component locations.

Source: Wipaire and the maintainer (inset), annotated by the ATSB

The landing gear indication panel, to the right of the pilot’s seat (at the base of the control column), contained 10 lamps. Four blue to indicate the 2 nose and 2 main gear were up, 2 red to show hydraulic pump operation and 4 amber to indicate the gear was down. In addition to the standard equipment, VH‑OHU was also fitted with a hydraulic pressure gauge for pilot reference (Figure 6). 

Each gear actuation operates independently (no set sequence) and therefore, the main gear UP and DOWN lamps are progressively activated by proximity switches, when the respective latch hook nests over the locking pin. The red hydraulic pump lights should extinguish shortly after all 4 UP or DOWN lamps are illuminated.

The airplane flight manual supplement for the amphibian floats described ‘bulb replacement during flight’. Where a lamp is not illuminated as expected, the pilot can readily remove the lamp and a known functioning lamp can be inserted into that location. This allows the pilot to determine if the non-illumination is a defective bulb, or other system issue. 

Figure 6: Typical landing gear panel
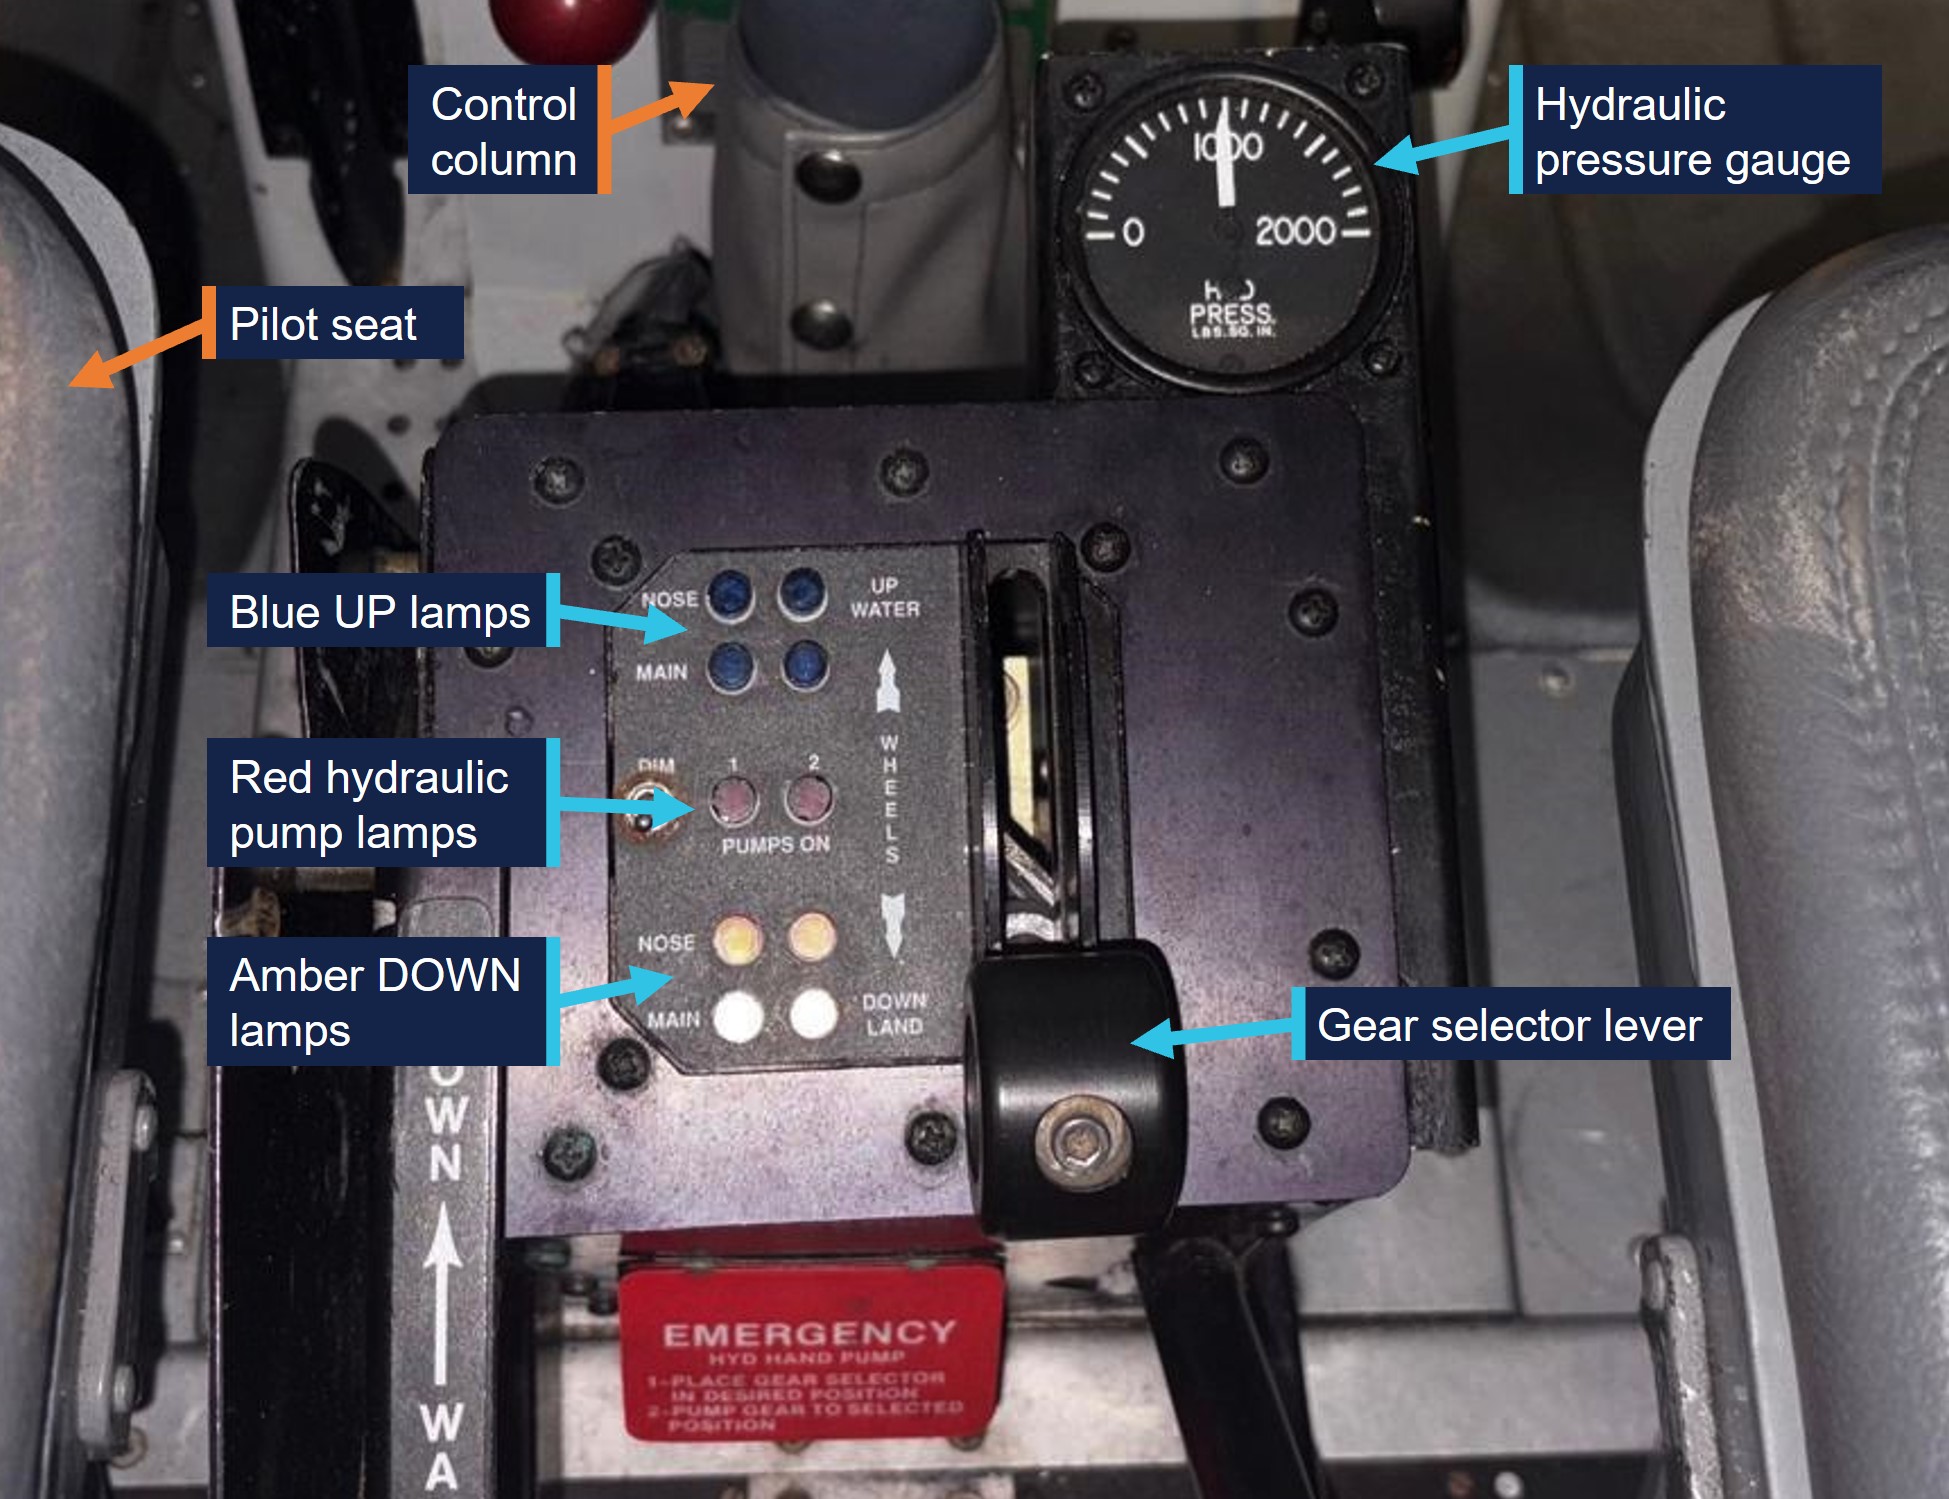
Image of a typical landing gear panel showing location of lamps and selector lever.

Source: Used with permission, annotated by the ATSB

The airplane flight manual supplement for the amphibian floats included the following:

Warning re amphibian floats - text reproduced from the flight manual supplement

The supplement further included that, where cycling of the gear does not rectify an asymmetric condition, rather than landing on water, the preferred option is to conduct the landing on a hard surface or grass:

Landings of this sort produce little tendency to nose over when checklist procedures are used, even when conducted on hard surface runways, and will result in little or no damage to the floats.

Mirror

In addition to the landing panel gear position indication, the aircraft was also fitted with an optional mirror, installed on the left wing (Figure 7). Wipaire advised the mirror was not part of its float modification, however, it was aware it was a common addition to float planes. 

This mirror allowed the pilot in the left seat to view the position of all 4 gear. This was particularly effective to confirm if the right main gear was retracted or extended from the underside of the right float, which was not possible without the mirror. The company pilots the ATSB spoke with reported varying opinions on the effectiveness for observing the right main gear via the mirror (see Operational information). However, all reported the mirror on the aircraft was correctly aligned following the recent maintenance and was effective in determining gear position.

Figure 7: Left wing mirror location, with representation of extended gear visible view

Image of a DHC-2 showing location of the left wing mirror.

Source: Used with permission, annotated by the ATSB

Amphibian gear advisory system

The aircraft was also fitted with a Wipaire-authorised amphibian gear advisory system (AGAS), which provided the pilot with supplementary gear position information. Following departure, once the aircraft increased through a threshold airspeed, the system was armed. Upon slowing down through the threshold airspeed, in preparation for landing, the AGAS ‘Gear Advisory’ amber lamp (Figure 8), positioned on the instrument panel in front of the pilot, would illuminate. In addition, an audio annunciation, heard through the front seat headset/s, would commence. Where all 4 gear were retracted, the annunciation would consist of ‘gear up for water landing’ (female voice). Conversely, where all 4 gear were extended, the annunciation would be ‘gear down for runway landing’ (male voice). The audio annunciation would repeat every few seconds, until silenced by the pilot pressing the gear advisory lamp. The annunciation was a prompt for the pilot to check their gear configuration was correct for the intended landing surface.

Figure 8: Example of location of gear advisory lamp in DHC‑2 instrument panel

Typical DHC-2 instrument panel showing location of gear advisory annunciator lamp.

Note: the insert is taken from the AGAS airplane flight manual supplement. Source: Used with permission, annotated by the ATSB

The AGAS also had a ‘check gear’ advisory. In this case, when the aircraft slowed through the threshold airspeed, the gear advisory amber lamp would illuminate and the annunciation of ‘check gear’ would be heard in the same female voice and similar tone as that for the ‘gear up for water landing’ advisory. There were no additional tones associated with this alert. Check gear indicated an asymmetric condition in the landing gear, where one or more proximity switches had not closed. This was designed to prompt the pilot to abort the landing and troubleshoot the discrepancy. The airplane flight manual supplement for the AGAS included the warning:

Warning text reproduced from airplane flight manual supplement for the AGAS

In addition, to ensure the system was functioning prior to flight, the ‘operational checklists’ detailed the ‘before take-off’ checks as:

  • annunciator switch – PRESS and HOLD for 2-3 seconds
  • test audio – VERIFY message is audible
  • annunciator switch – VERIFY annunciator light flashes.

Wipaire advised that the ‘test’ audio check contained the gear up and gear down messages only. That is, the check gear annunciation was not included in the system test audio.

Wipaire maintenance documentation

The Wipaire instructions for continued airworthiness (ICA) described the general servicing of the floats and landing gear. The manual also included the following warnings to ensure corrosion from saltwater operations was kept to a minimum:

Text from Wipaire manual - warning to ensure corrosion from saltwater operations was kept to a minimum:

…

Text from Wipaire manual - warning to ensure corrosion from saltwater operations was kept to a minimum:

The ICA 25-hour maintenance requirements for the landing gear included washing the aircraft and floats with fresh water and inspecting surfaces and hardware for signs of corrosion, especially with saltwater use. In addition to specific nose gear maintenance actions, the main wheel bearings and main gear carriages were to be greased. This maintenance on VH‑OHU was typically conducted by the maintainer. The maintenance documentation recorded that a 25-hour float inspection was conducted by the maintainer on 5 October 2024, about 15 hours since the issue of the maintenance release.

The ICA inspection time limits and checklist section did not include a specific check for corrosion on the slide tube. Wipaire advised it was covered in the servicing section for ‘movable parts’, which detailed the inspection:

For lubrication, servicing, security of attachment, binding, excessive wear, safe-tying, proper operation, proper adjustment, correct travel, cracked fittings, security of hinges, defective bearings, cleanliness, corrosion, deformation, sealing and tension.

The 25-hour inspection was conducted with the aircraft on extended landing gear. In this configuration, the forward end of the slide tube could be inspected. However, the carriage assembly was positioned at the aft end of the slide tube, preventing inspection at this location. A gear retraction test, to check for correct operation of the gear up and down lock hooks, was to be conducted at 200-hour intervals. With the gear retracted, this then provided the opportunity to inspect the aft end of the slide tube.

Wipaire published service letter #80 AT-802 Fire Boss Slide Tube Corrosion in 2006. It described reports from operators of ‘sticking main gear actuators due to corrosion on the slide tube’. It noted that the corrosion was partially caused by gravel or debris from the main landing gear tyres eroding through the hard anodised surface of the slide tube, exposing the underlying aluminium, which was more susceptible to corrosion. Part of compliance included inspecting the slide tube for erosion and/or nicks and wiping the slide tube down with a clean rag soaked in lubricant. Wipaire advised there was no specific service letter to address corrosion for the 6000/6100 series floats.

Pilot maintenance

Due to the salt laden environment and exposure to seawater, the operator reported washing the aircraft with fresh water at the end of each operating day. In addition, greasing of the nose and main gear components, and other aircraft care activities, were periodically carried out. These additional tasks were to be carried out by an appropriately trained pilot, however, it was not recorded on the maintenance release or other formal record. It was also noted that there was no practice of washing the aircraft if it had not been operated for several days. 

The maintainer conducted the pilot maintenance training, demonstrating the additional maintenance tasks. The pilot of VH‑OHU had not yet received the formal training prior to the accident but advised that they had been shown these tasks by their training pilots.

Meteorological information

The meteorological conditions reported by the pilot at the time of accident were consistent with the Bureau of Meteorology forecast, with east-south-east winds of about 7–8 kt and good visibility. In addition, the pilot’s report and passenger footage showed the water conditions were ideal for float plane operations and sun glare was not angled into the cockpit and across the instrument panel.

Wreckage information and component examination

The ATSB did not attend the accident site or wreckage examination in Mackay, instead the ATSB liaised with the maintainer and the maintenance organisation that conducted the post-accident examination of the landing gear. The ATSB also reviewed images and video footage taken during these examinations.

Initial examination

The maintainer examined the aircraft, in the presence of the insurance representative, after it was retrieved from the ocean and provided the following observations regarding the landing gear system:

  • the aircraft was significantly disrupted during the retrieval from the water, including damage to the landing gear panel, which prevented the landing gear selector position to be definitively established
  • the landing gear appeared undamaged
  • hydraulic fluid was drained and appeared to be of expected quantity, with no water contamination
  • the 4 blue lamps were removed for testing, however, their location prior to removal was not recorded
  • one of the blue lamps failed testing, however, it could not be determined if this was from seawater immersion or a pre-existing fault.

The wreckage was then transferred to Mackay for storage and further examination.

About 2 weeks after the accident, the landing gear was examined by the maintainer and an engineer from another CASA-authorised maintenance facility. They provided a report to the ATSB, with following general observations:

  • hydraulic pump 1 and 2, AGAS and gear lamps circuit breakers were engaged, indicating the system was operating as expected
  • it was not possible to carry out a continuity and functional check of the gear panel indication system due to corrosion and moisture from saltwater ingress
  • fuses for pumps 1 and 2 ‘ON’ lamps tested serviceable
  • both nose gear assemblies and the left main gear were observed to be up and locked, indicating a complete retraction
  • the right main gear was extended
  • some corrosion was noted on the forward face of both the left and right carriage assembly to slide tube interface.

The maintainer advised the ATSB that, when they tried to move the left main gear carriage, it initially did not move. However, ‘a small knock with a hammer freed the carriage’, which then moved freely. The carriage was likely held up by the observed minor corrosion at the slide tube interface. Further, there was ‘little to no damage’ on the slide tube, compared to the same location on the right slide tube.

Right main gear examination

Detailed examination and testing of the right main gear assembly was then conducted. The report included the following observations: 

  • the down hook was found to be free of the locking pin (unlocked)
  • the right main gear was approximately 1.5–2 mm from fully down
  • gear position light proximity switches tested for resistance to ground with no issues
  • continuity testing of the proximity sensor switches showed UP and DOWN ‘open’, which was correct for the current configuration (gear mid travel).

Hydraulic pressure was then applied to the right main gear using a hand pump and calibrated pressure gauge. With 870 psi applied in the retraction direction, the carriage did not move along the slide tube. This was despite progressively adding oil to the slide tube/carriage interface, supplying grease to the carriage, disconnecting the shock strut and applying mechanical assistance via a pry bar.

The hydraulic pressure supply was then transferred to the extend direction. The carriage and slide tube moved together and closed the 1.5–2 mm gap. With this actuation, the actuator piston moved relative to the carriage assembly and the DOWN lock engaged as per design specifications. Testing of the proximity switch showed it to be closed, correct for the configuration. The direction of hydraulic pressure was reversed to retract and the DOWN lock was observed to disengage freely, with the proximity switch again testing correctly.

The report noted that at no time did the carriage move relative to the slide tube during the testing, establishing that the carriage assembly was seized on the slide tube. When the slide tube was removed from the float, a slide hammer and block of wood was successful in separating the carriage assembly from the slide tube. A significant amount of corrosion was then noted on the slide tube.

The ATSB then requested the left and right slide tubes and carriage assemblies be provided for further examination.

Component examination

The ATSB and Wipaire conducted testing and analysis to try to determine the circumstances that allowed the corrosion to develop. Examination of the left and right slide tubes and carriage assemblies was conducted at the ATSB’s technical facilities in Canberra, Australian Capital Territory.

The right slide tube had 2 bands of corrosion that corresponded with the bushing locations in the carriage, at about the fully extended location (Figure 9). The left slide tube showed no similar damage. Both carriage assemblies exhibited grease around the UP and DOWN hooks and internally. The components were not serialised, so the history of the carriages prior to the aircraft entering Australia could not be determined.[4] 

Figure 9: Comparison of slide tubes, showing corrosion bands on the right slide tube (on the right) and location of bushings examined by the ATSB
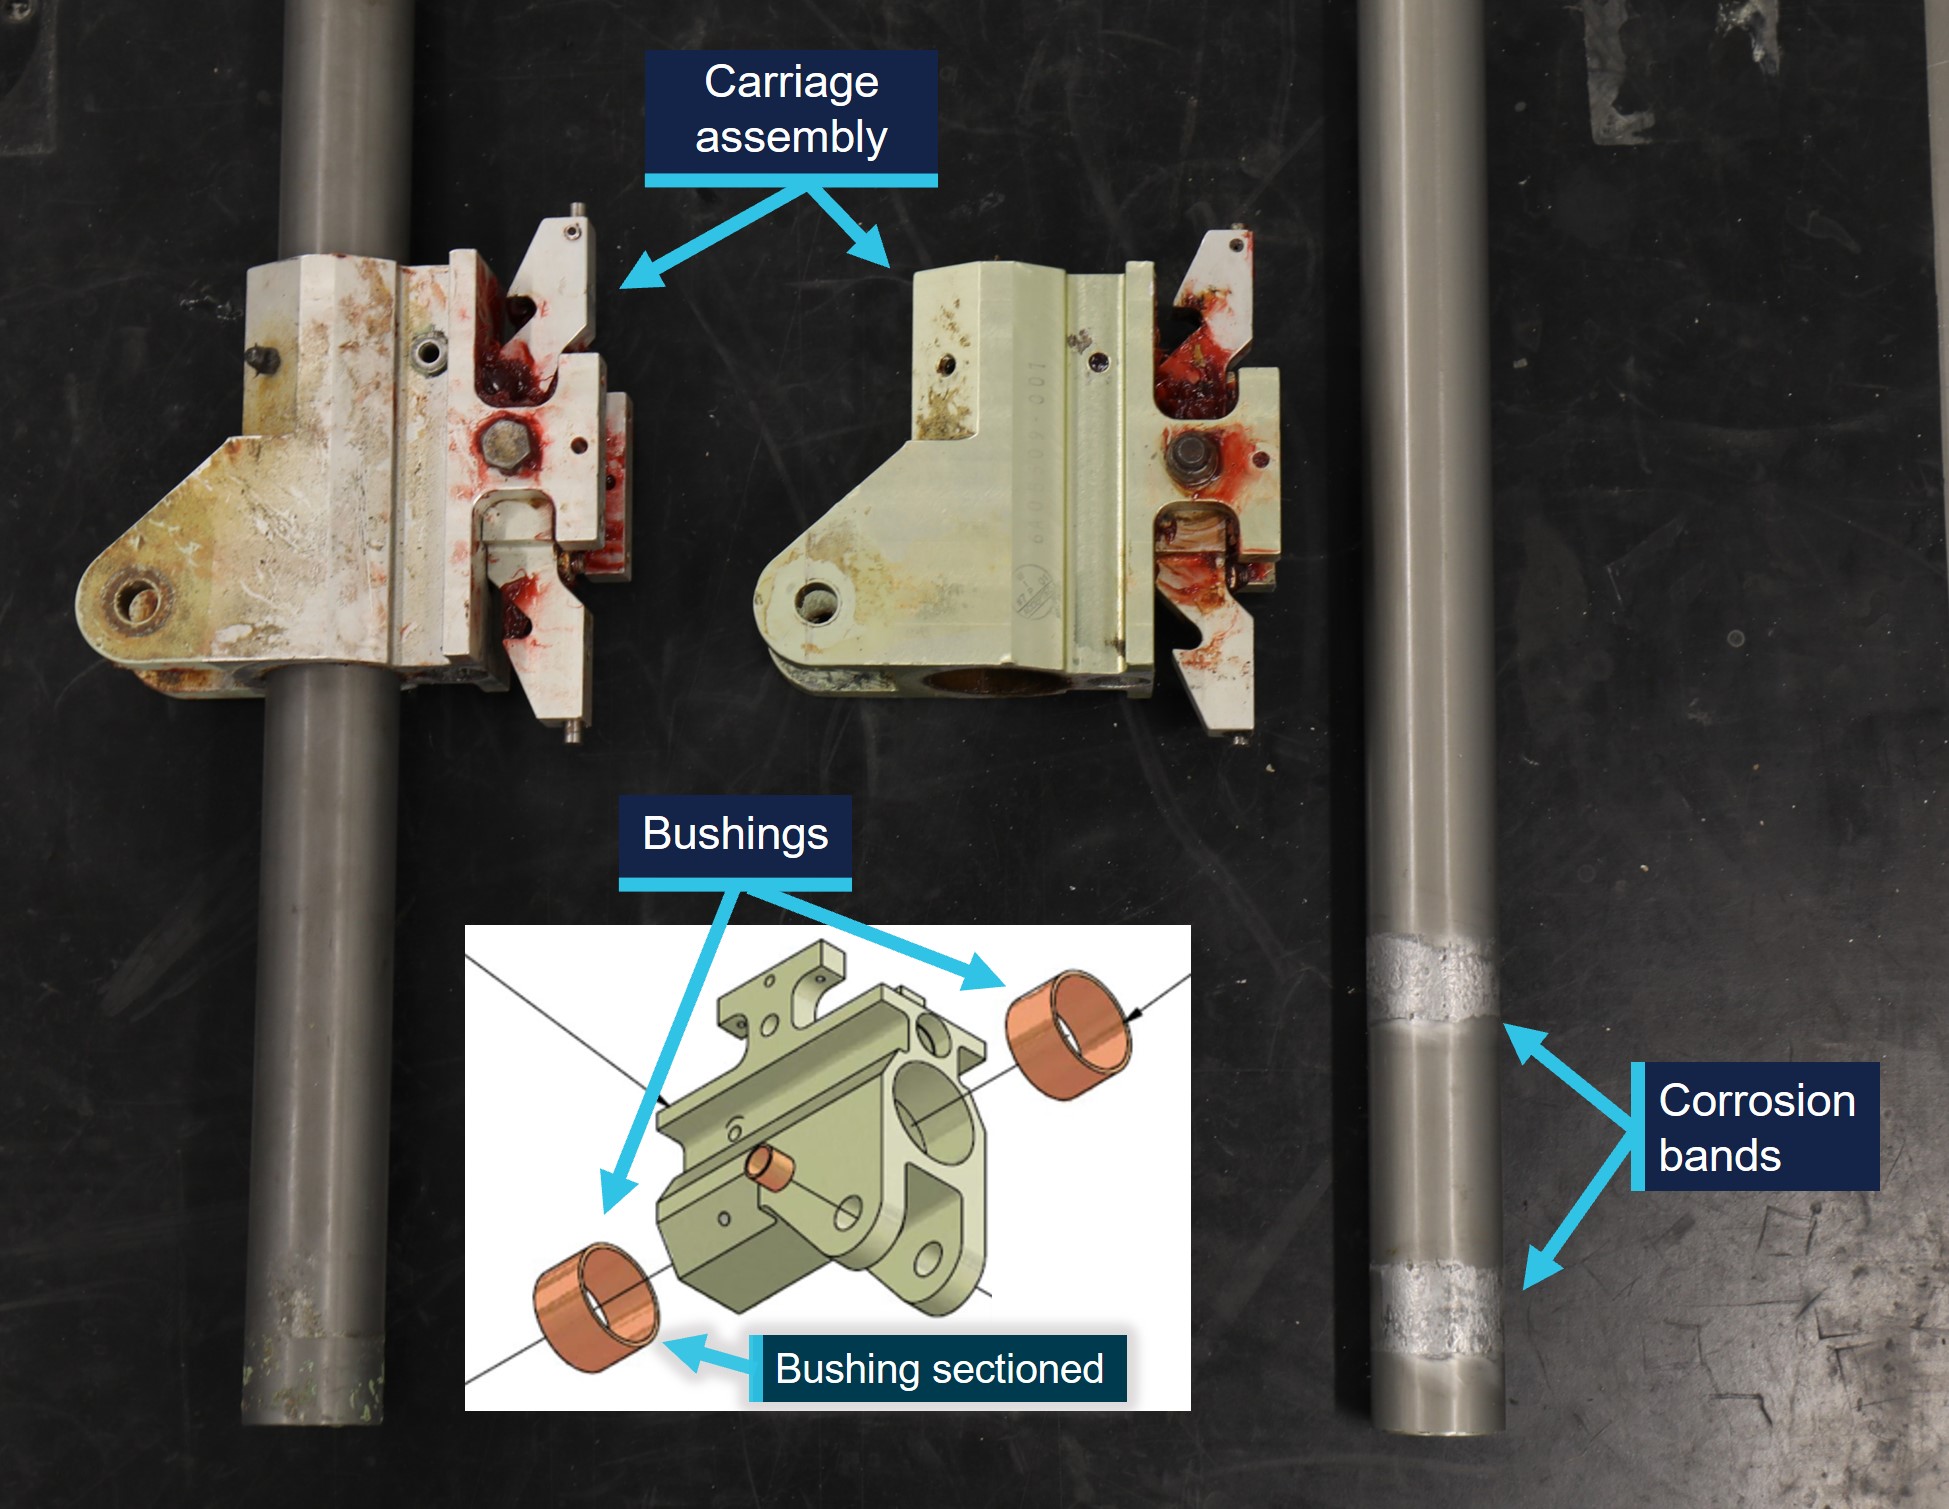
VH-OHU slide tube and carriage assemblies, showing bands of corrosion on right slide tube.

Source: ATSB and used with permission, annotated by the ATSB

Detailed examination of the components was then conducted, with reference to the Wipaire-supplied specifications.

The slide tubes were manufactured from aluminium with an anodised coating. The slide tube dimensions were measured to be within specifications and the anodised layer was the correct thickness. The slide tube surface was non-conductive, as expected for an anodised layer.

The bushings were a tri-layer construction, with a base layer of steel, with sintered (porous) bronze and then coated in a PTFE[5] ‘sliding layer’. The bushing could be replaced and therefore, the carriage time in service did not necessarily correspond to the bushing time in service. The bushings of both carriages were examined, with observations including the internal diameters of all bushings were within drawing tolerances and the right bushings were more worn than the left (Figure 10).

Figure 10: Difference in bushing wear with the left (left) showing largely intact PTFE layer (grey) and right (right) showing significant exposure of the sintered bronze layer

Close up of left and right carriage assembly bushings showing wear PTFE layer.

Source: ATSB

The right carriage bushing located near the grease nipple was sectioned. Examination identified areas where the PTFE layer was not present, exposing the bronze layer and showing some evidence of scoring (Figure 11). The PTFE layer was non-conductive in contrast to the bronze.

Figure 11: Right carriage bushing surface showing Teflon/lead layer (grey), exposed bronze layer (copper) and some evidence of scoring (bright lines)

Close-up of right carriage assembly showing worn PTFE layer exposing bronze layer

Source: ATSB

The slide tube corrosion patterns were consistent with galvanic corrosion between the exposed bushing bronze layer and the aluminium slide tube base metal, in the presence of salt from coastal operations. The difference in wear between the left and right carriage bushings likely influenced the degree of corrosion on the respective slide tubes. The bushings with a higher amount of retained, non-conductive PTFE layer showed significantly less corrosion on the corresponding slide tube.

The ATSB determined that there were no material or manufacturing issues identified with the slide tubes, and therefore the thin, hard anodised coating was likely damaged or worn through in this area, to allow for the dissimilar metal contact. This type of damage was also observed in discrete locations in deeper score marks on the slide tube, away from the main areas of corrosion. 

Damage to the anodise was unlikely to have been directly from the worn bushings, since the bronze is softer than the hard anodise layer, but it was possible for dirt, sand or other abrasive debris to have become entrapped between the bushings and slide tube. While there was no significant entrapped material identified during the ATSB examination, the mechanism was shown to exist, as described in Wipaire service letter #80. 

Operational information

Operator overview

Whitsunday Air Services, trading as Hamilton Island Air, conducted tourist charter flights to various locations in the Whitsundays, Great Barrier Reef and Hamilton Island areas, using a variety of fixed-wing and helicopter types. At the time of the accident, it operated a fleet of 17 helicopters and 3 fixed-wing aircraft: VH‑OHU, a GA8 Airvan and a Cessna 208.

Training pilot observations

The operator had an appointed fixed-wing specialist, who oversighted the fixed-wing operations and pilot training. The fixed-wing specialist (training pilot 1 – TP1) had advised the operator their intention to depart the organisation in September 2024. In August, they commenced correspondence with the accident pilot, in preparation for their employment and training. 

TP1 collected VH‑OHU from the maintenance organisation in Mackay. Due to the aircraft coming out of extended maintenance, and TP1 having not operated it for a period of time, TP1 reported conducting a series of test flights, including water landings near Mackay and then en route to Hamilton Island. TP1 reported that the landing gear and AGAS were operating as expected. In addition, TP1 advised the mirror was correctly oriented to view all 4 gear. TP1 then commenced training the accident pilot on VH‑OHU, between 10 and 20 September 2024, before leaving the organisation. 

Training was then conducted by the current fixed-wing specialist (training pilot 2 – TP2), from 5 October 2024. The training again included land and water landings, with TP2 advising the landing gear and AGAS systems were functioning correctly. TP2 advised the left mirror was correctly oriented, however, the right main gear could sometimes be difficult to distinguish from the background contrast (such as terrain, sky, water). TP2 reported their preference for having an additional right-side mirror, and they were in the process of procuring a second mirror at the time of the accident.

Pilot recollections
Accident day

With regard to the day of the accident, the pilot reported:

  • they did not feel any operational or time pressure
  • they were comfortable with operating the aircraft solo, and with passengers
  • the landing area only contained a few vessels, therefore, workload was not increased
  • there were no distractions from the passengers during the approach to land and landing
  • while there was a checklist available, the pre-landing checks were completed from memory, which was permitted by the operator’s procedures
  • they observed 4 blue lights indicating the gear was up for a water landing
  • they checked the mirror
  • they did not recall hearing the AGAS annunciator just prior to landing
  • during the accident sequence the aircraft flipped ‘within a second and I was underwater, upside down, almost instantly submerged, no air at all’.

Following the aircraft becoming submerged inverted, the pilot advised that, due to their recent helicopter underwater escape training, they ‘came right into action’ and ‘wasted no time’. The pilot advised that they would recommend the training to pilots operating sea planes or ‘any planes over water’.

Further, the pilot reported that, had they observed the extended right wheel, they would not have conducted the water landing, and would have returned the aircraft to Hamilton Island for a runway landing.

Training and aircraft systems

The pilot reported that they were happy with their training from both training pilots. In addition, they did not perceive any difficulties with training on the DHC‑2 and GA8 Airvan concurrently. 

When discussing the mirror, the pilot described its importance in determining gear position. However, they also reported that there might be a blind spot that means the right main gear may be difficult to see.

When asked by the ATSB if the AGAS self-test was successful prior to the accident flight, the pilot reported to not being aware of this procedure. The pilot also reported to not have heard the AGAS ‘check gear’ annunciation during their training.

Seaplane operations guidance

The Seaplane Pilots Association published guidance on amphibious gear management best practices, to ‘enhance safe operations within the seaplane community’.[6] The guidance advocated the use of checklists and described triggers or cues, with each phase of flight, ‘to deter landing with the gear in the wrong position’. The ‘on water-based landing’ section included, in part:

  • several gear-position validation checks, during initial flyover, pre-landing operations (1st power reduction, setting flaps et cetera) and establishing on final approach to land
  • verbalise each gear position validation while visually confirming
  • pay attention to the gear advisory system, if installed.

In addition, the guidance stated, ‘it is very important to crosscheck the surface intended for landing with the gear position selected and where the gear actually is positioned’ and included:

As general guidance, an amphibious aircraft should be considered more vulnerable to a catastrophic accident, which may include serious injury and death, with the gear down. While all efforts should be taken to avoid landing on either a runway or a waterway with the gear in the wrong position, landing on a runway with the gear up tends to be much more benign, with minimal damage and injuries, compared with landing on water with the gear down. Avoiding either scenario is best done by being attentive and not complacent.

Survival aspects

Helicopter underwater escape training (HUET)

HUET has been in use around the world since the 1940s and is considered best practice in the overwater helicopter operating industry. HUET is designed to improve survivability after a helicopter ditches or impacts into water. Fear, anxiety, panic and inaction are the common behavioural responses experienced by occupants during a helicopter accident. In addition to the initial impact, in-rushing water, disorientation, entanglement with debris, unfamiliarity with seatbelt release mechanisms and an inability to reach or open exits have all been cited as problems experienced when attempting to escape from a helicopter following an in-water accident (Rice and Greear, 1973).

The training involves a module (replicate of a helicopter cabin and fuselage) being lowered into a swimming pool to simulate the sinking of a helicopter. The module can rotate upside down and focuses students on bracing for impact, identifying primary and secondary exit points, egressing the wreckage and surfacing.

The ATSB has previously emphasised the importance of HUET for all over-water helicopter operators in other investigations including AO-2018-022, AO-2019-008, AO‑2020-003 and AO-2023-044. Further, HUET is included in the ATSB’s Safety Watch Reducing the severity of injuries in accidents involving small aircraft.

Safety briefing 

The ATSB viewed the safety briefing video and noted it described the operation of door handles from across the operator’s fleet, although the aircraft associated with each handle was not explicitly stated. When the ATSB discussed the briefing process with the passengers, they recalled that the video had a lot of different door handles. One passenger also noted the video seemed to be focused more on helicopters, rather than the floatplane. However, the passengers recalled the pilot briefing them at the aircraft and showing them how the door handles worked on VH‑OHU.

Emergency egress

In this accident, the passengers required assistance from the pilot to egress from the submerged aircraft. Had the pilot been unable to assist, the outcome may have been more severe.

This possibility was reported by the Transportation Safety Board of Canada (TSB) in investigation A09P0397 Loss of control and collision with water involving a DHC‑2 on 29 November 2009. Following the collision with water, the pilot and one passenger survived, however, the other 6 passengers succumbed to injuries from immersion. The report included the following safety issue:

Over the last 20 years, some 70% of fatalities in aircraft that crashed and sank in water were from drowning. Many TSB investigations found that the occupants were conscious and able to move around the cabin before they drowned. In fact, 50% of people who survive a crash cannot exit the aircraft and drown.

The TSB recommended ‘the Department of Transport require that all new and existing commercial seaplanes be fitted with regular and emergency exits that allow rapid egress following a survivable collision with water’ (A11-05).

TSB report A18A0053 Loss of control and collision with water, involving a DHC‑2 on 11 July 2018 noted the aircraft became inverted during the accident sequence. One pilot escaped through the broken front windscreen. The other pilot was unable to open their forward right door nor the cabin door, however, the first pilot was able to open the cabin door from the outside. Neither pilot had undergone emergency egress training, nor was it required. Further, the report included:

Emergency door release mechanisms, better door handles, and push-out windows have been developed for certain types of floatplanes. Some floatplane operators have installed these modifications, but many have not. 

Regulatory requirements for mandatory egress training for commercial floatplane pilots may result in some improvement in emergency egress from commercial seaplanes. However, if the regulator does not mandate or promote voluntary modifications to normal exits, seaplanes will continue to operate with exits that could become unusable following an impact, diminishing the chance occupants have to exit the aircraft following a survivable accident.

Push-out windows

Viking Air Limited (the type certificate holder at that time, now held by De Havilland Aircraft of Canada, see Aircraft information) developed ‘push-out windows’ (Figure 12) and published service bulletin V2/0003 New cabin door windows that incorporate a ‘push-out’ feature in July 2010. The service bulletin noted:

- A series of incidents involving float equipped aircraft has highlighted the need to improve emergency egress from the cabin.

- The Cabin Door Push-Out Window Kits contain a rubber-mounted right-hand and/or left‑hand passenger window which affords additional egress opportunities from the aircraft.

- Viking has designed new windows for the passenger doors that incorporate the same ‘push-out’ feature used for many years on helicopters operating overwater.

- Viking Air Limited strongly recommends that this safety improvement be incorporated on aircraft operating on floats and any wheeled aircraft operating over water, or as directed by the operator’s Regulatory Authority.

Figure 12: Example of main cabin door push-out window

Example of a push-out window installed in a DHC-2

Source: De Havilland Aircraft of Canada and Naomi Lacey (inset), annotated by the ATSB

De Havilland Aircraft of Canada advised it has supplied about 130 kits worldwide, with one kit to Australia. VH‑OHU was not fitted with the push-out windows, nor was it required by regulations.

Revised door latches

Viking Air Limited published service bulletin V2/0004 Installation of an automotive style cabin door latch system in November 2010. The service bulletin cited the reason as ‘the dual automotive (pull) style cabin door latch system provides better egress from the cabin in the event of an emergency’ (Figure 13). The service bulletin also noted:

- Viking Air Limited (Viking) has designed a dual automotive (pull) style cabin door latch system that is more familiar and intuitive to passengers. The existing single latch handle (rotating style) at the rear of the door has been replaced by one pull style latch handle at the same location and a second pull style latch handle in the forward portion of the door. This allows passengers in the forward and rear cabin seats to open the cabin doors in an emergency situation.

- Viking strongly recommends that this safety improvement be incorporated on all DHC‑2 aircraft or as directed by the operator’s Regulatory Authority.

De Havilland Aircraft of Canada advised it had supplied 70 door latch kits to date. VH‑OHU was not fitted with the modified door latch system, nor was it required by regulations.

Figure 13: Representation of revised door latches, with VH‑OHU door in inset
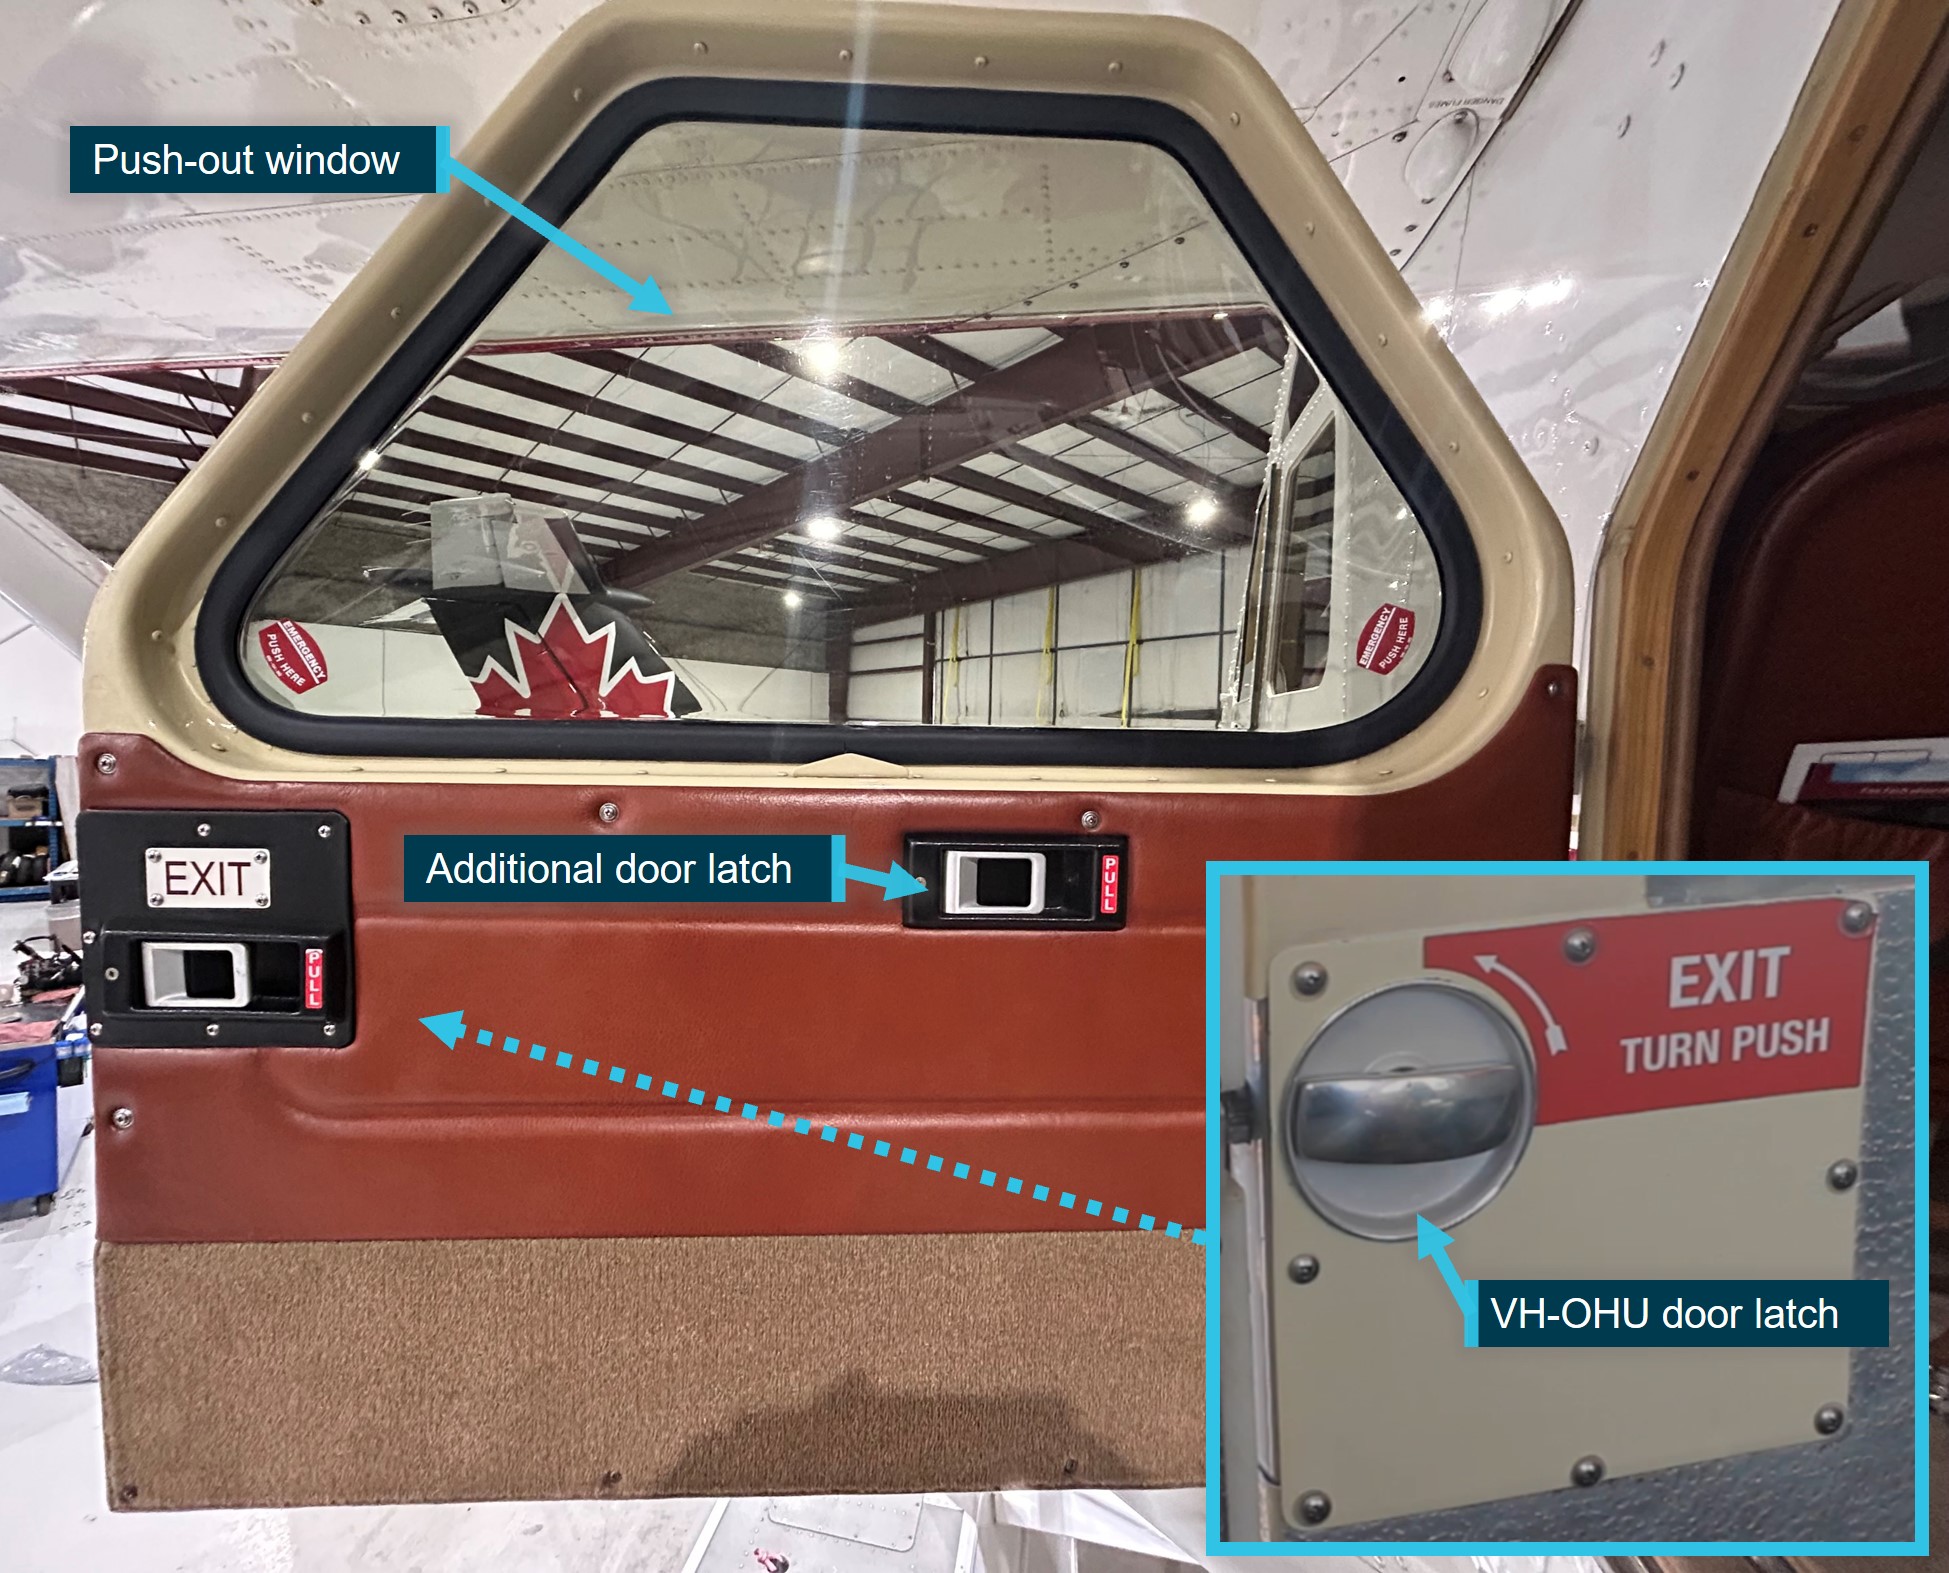
Example of revised door latches for a DHC-2

Note: the rotational-style door latch, as was in VH‑OHU, operates in one direction only. Source: De Havilland Aircraft of Canada and the operator, annotated by the ATSB

Similar occurrences

There have been a number of occurrences involving DHC‑2 where one or more wheels were extended during a water landing resulting in the aircraft nosing over and becoming inverted. This has been evidenced in several United States National Transportation Safety Board (NTSB) accident reports as summarised below.

N218RD at Oak Island, Minnesota, on 22 May 2021 (CEN21LA244)

The aircraft departed with a known hydraulic leak in the landing gear system. During the flight, the degraded hydraulic system resulted in the inadvertent extension of the left main gear. This was not identified by the pilot and the aircraft nosed over upon landing on the water and became inverted. The pilot and one passenger were not injured, and one passenger sustained serious injuries.

N9558Q at Stehekin, Washington, on 17 May 2008 (LAX08FA144)

The pilot did not raise the landing gear after take-off. The pilot also reported the flight was turbulent and bumpy, with slow airspeed due to the heavy load. This resulted in numerous AGAS annunciations, until the pilot pulled the circuit breaker to disable the ‘nuisance’ alerts. The pilot intended to reset the AGAS prior to landing but did not do so. When the aircraft landed on the water with the wheels extended, it abruptly nosed over and became inverted. The pilot and 2 passengers survived, and 2 passengers were unable to exit the aircraft and succumbed to immersion. 

N60TF at Sitka, Alaska, on 30 May 2003 (ANC03LA054)

The pilot advised they forgot to raise the landing gear following departure from land. During the water landing, with the wheels extended from the floats, the aircraft nosed down in the water. The pilot was uninjured.

N4478 at Aleknagik, Alaska, on 28 August 2002 (ANC02FA106)

The NTSB found the pilot did not raise the landing gear following departure from land. During the water landing, with the wheels extended from the floats, the aircraft nosed over and became inverted. The 2 passengers escaped with minor injuries and the pilot sustained fatal injuries attributed to immersion.

Safety analysis

Introduction

On the morning of 26 October 2024, the pilot of a De Havilland Aircraft of Canada DHC‑2, registered VH‑OHU, departed Hamilton Island aerodrome, Queensland, with 4 passengers on board for a short scenic flight to Whitehaven Beach, Whitsunday Island. Upon touching down on the water, the aircraft yawed to the right, nosed over and became submerged inverted. The pilot and 4 passengers sustained minor injuries and the aircraft was substantially damaged.

This analysis will discuss the right main gear failing to retract, the unsafe configuration not being identified by the pilot and delayed egress of the passengers. In addition, the analysis will consider why the pilot did not hear the gear annunciation. Further, the pilot’s recent underwater escape training and availability of enhanced egress aircraft modifications will also be discussed.

Right main landing gear failed to retract

Immediately following the accident, the right main gear could be seen extended from the float. Examination of the aircraft found no evidence of leakage, loss or contamination of the hydraulic fluid, and all landing gear circuit breakers were engaged. Further, the nose and left main gear had successfully retracted, indicating the anomaly was likely isolated to the right main gear.

During retraction, the main gear travels aft as it swings up into the float. Had the gear been mid-travel, such as still cycling, the impact with the water would have forced the gear to retract up into the float. Therefore, it was unlikely the right main gear moved during the impact sequence. This was consistent with the post-accident examination, which identified that the right carriage assembly had seized on the slide tube at the almost fully extended position. 

Once removed from the aircraft, forceful removal of the carriage resulted in the identification of advanced corrosion on the right slide tube. The 2 bands of corrosion were coincident with the location of the carriage bushings, near the full gear extension position. This would be expected as the aircraft was predominantly parked on land, with the gear extended.

The investigation considered scenarios conducive to the formation of this corrosion. The maintenance records prior to the aircraft entering Australia in 2015 were not available, as such, the service history of the main gear carriage assemblies, including the bushings, was unknown. While there was a significant difference in the condition of the left and right slide tubes, both tubes were installed at the same time and therefore subject to the same operational and environmental conditions.

The operator advised the aircraft was rinsed with fresh water at the end of the operating day, however, this was not formally recorded and there was no practice for rinsing when the aircraft was not operated for several days. The aircraft records showed the maintainer conducted a 25-hour float inspection on 5 October 2024 and grease was observed on the assemblies during post‑accident examination. However, as there was no requirement to retract the gear for this inspection, the position of the carriage assembly precluded visual examination of the slide tube at the location where the corrosion had developed.

Examination of the carriage bushings identified that the right bushings exhibited more wear and loss of the PTFE ‘sliding layer’, which runs along the slide tube. This had the potential for galvanic corrosion to form, however, required the degradation of the anodised layer on the slide tube to also be present. Insufficient cleaning, inadequate application of grease and/or accumulation of dust or dirt on the slide tube are known contributors to degradation of protective layers. While the extent to which they were contributory in this case was not able to be determined, it was likely that the identified corrosion resulted in the right main gear seizing.

Pilot did not identify extended right main gear

The pilot reported observing 4 blue ‘gear up’ lamps illuminated, at about Tongue Point, and during their pre-landing checks. The passenger footage showed sun glare was not angled in the direction of the landing gear panel and the pilot advised they were able to clearly identify what lamps were illuminated. However, when tested post‑accident, one blue lamp did not illuminate, although it could not be determined if this failure was due to seawater immersion or pre-existing. Further, the location of the failed lamp could not be determined as the lamps were not identified on removal from the landing gear panel. Despite this, failure of any lamp to illuminate requires troubleshooting by the pilot prior to landing. The pilot can readily determine if the lack of illumination of a lamp is due to a failed bulb or other system issue. 

The main right gear UP and DOWN proximity switches tested serviceable during the post-accident examination. The examination also noted the right main gear had unlatched from the DOWN location and moved about 1.5–2 mm in the retract direction before becoming seized. During the landing gear retraction sequence, pressure in the hydraulic system would increase until the pumps automatically switched off and the red ‘in-transit’ lamps would extinguish. In this configuration, with nil movement in the right main gear due to the seizure, it was expected that only 3 blue lamps would have been illuminated. Therefore, the investigation could not reconcile the pilot’s recollection of there being 4 blue lamps illuminated.

The mirror provided an additional method to identify the landing gear configuration. Training pilot 1 advised they could observe all wheels in the mirror following the aircraft repairs. Training pilot 2 reported sometimes experiencing difficulty in observing the right main wheels from the mirror. The accident pilot reported a blind spot, which hindered their ability to see the right main gear in the mirror. However, during the pre‑landing checks, the accident pilot reported they checked the mirror and did not observe any wheels protruding from the floats and continued with the water landing.

Another method to identify the gear position was via the amphibian gear advisory system (AGAS), which provided a visual and audio annunciation as the aircraft slowed for landing. The pilot had been communicating via the radio with the helicopter pilot, thereby showing the audio system in VH‑OHU was operational and that the AGAS annunciation was able to be heard through the headset. However, the pilot reported they could not recall hearing any annunciation prior to landing on the water. Due to disruption of the floats during the accident, the system could not be functionally tested. The pilot advised they were not aware of the pre-flight self-test of the AGAS and therefore this was not conducted prior to the accident flight. While it remained a possibility that the AGAS did not alert the pilot to an asymmetric condition prior to the landing, all 3 pilots reported the AGAS had been functioning correctly in the preceding weeks. Therefore, while it could not be conclusively determined, it was more likely the system was operational.  

The pilot’s 84 water landings in VH‑OHU did not necessarily represent the number of times they had actuated the landing gear, however, they did select the gear to retract after departing Hamilton Island. In addition, the pre-landing checks required the pilot to utilise the aircraft systems to ascertain gear position prior to each landing, regardless if the gear was cycled. Further, the pilot also reported no issues with distractions, workload or experiencing time pressures. 

Therefore, while the aircraft was fitted with multiple systems to confirm the status of the landing gear, for undetermined reasons the pilot did not identify that the configuration was unsuitable for a water landing. This resulted in the aircraft yawing to the right, nosing over and becoming submerged and inverted, a known consequence of water landings with one or more gear extended.

Landing gear annunciator 

The pilot advised the ATSB that they did not recall hearing the AGAS annunciation just prior to the landing. The ATSB’s analysis concluded the AGAS was more likely than not operational at the time of the accident. The investigation therefore considered potential reasons for the audio alert not being heard or being dismissed.

The ‘gear up for water landing’ and ‘gear down for runway landing’ are advisory only and an opportunity for the pilot to check the gear selection matches their intended landing surface. In contrast, the ‘check gear’ annunciation was alerting the pilot that the 4 gear were not all fully up or down and in an unsafe configuration for landing. However, the ‘gear up’ and ‘check gear’ both used a similar female voice and there were no additional tones to indicate the heightened importance of the ‘check gear’ alert. Further, when below the threshold airspeed, the amber ‘gear advisory’ lamp would illuminate, irrespective of the gear configuration. 

The purpose of auditory warnings is to attract attention to a problem (Salvendy & Karwowski, 2021). Ideally, advisory annunciations would sound distinctly different to other alerts to assist pilots to recognise there is problem requiring their action. Making alerts distinctive from other sounds can also inform the pilot of the priority or urgency of the problem (Yeh et al. 2016, FAA, 2016). During approach to land, with the gear in an asymmetric configuration, the AGAS would have enunciated ‘check gear’, indicating an unsafe condition. 

As the pilot would have expected to hear an annunciation with a female voice during landing, there was little to distinguish it from an alert that required action. In addition, the pilot reported they had not heard the ‘check gear’ alert during the training, reinforcing the female annunciation was to be expected and normal. This increased the risk that a pilot would not recognise that the landing gear was in an unsafe condition and removed an opportunity to consider a runway landing, the preferred option in this scenario. However, as the pilot reported not hearing any annunciation prior to landing, there was insufficient evidence to determine if the lack of distinction between the ‘gear up’ and ‘check gear’ annunciations contributed to the accident.

Passengers’ delayed egress

During the accident sequence, the aircraft rapidly filled with water, giving all on board little time to react. Despite being temporarily tangled in their seatbelt, the pilot readily exited the aircraft and swam to the surface. When no passengers appeared, the pilot swam back to the aircraft.

The 2 passengers seated next to the left rear cabin door reported they quickly released their seatbelts, and both attempted to open the door. The pilot was trying to open this door at the same time, without success. The 2 passengers recalled they attempted to locate the right rear cabin door, which was about coincident with the pilot’s decision to also try this door. The pilot managed to open the right rear door and assisted the passengers to the surface. 

The ATSB considered the circumstances that prevented the left rear door from being easily opened following the accident. It was possible that water pressure from the outside was greater than inside the cabin, until equalising as the cabin filled with water. Alternatively, distortion to the airframe during the impact sequence could have prevented door operation. While the reason could not be determined, this contributed to the delayed evacuation from the submerged aircraft.

Underwater escape training

The pilot had completed operator-required helicopter underwater escape training about one month prior to the accident. They attributed this training to their prompt escape from the inverted and submerged aircraft, and subsequent assistance to the passengers. As evidenced in previous ATSB investigations, this training has been shown to significantly increase the chances of survival in the event of a collision with water.

Enhanced egress aircraft modifications

Following multiple similar accidents where occupants initially survived but were subsequently fatally injured from immersion, the Transportation Safety Board of Canada recommended the fitment of regular and emergency exits that allowed rapid egress in the event of a collision with water. Consequently, Viking Air Limited developed push-out windows and more intuitive automotive-style door latches for the main cabin door. These modifications were not fitted to VH‑OHU nor were they required by regulations. 

In this accident, 2 of the passengers were actively searching for a means of escape, but ultimately required the pilot to open the door. However, if the pilot had been unable to assist, the accident could have resulted in dire consequences. Acknowledging that people behave differently in emergency situations, providing an alternative means of escape where one or more doors cannot be opened, increases the chance of survival. This is most relevant with submerged aircraft, yet can also expediate egress for land‑based accidents, particularly those involving a post-accident fire. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the landing gear malfunction and collision with water involving De Havilland Aircraft of Canada DHC‑2 Beaver, VH‑OHU, near Whitehaven Beach, Whitsunday Island, Queensland, on 26 October 2024. 

Contributing factors

  • Likely due to corrosion, the right main landing gear assembly seized near the fully extended position, which prevented retraction after take-off from Hamilton Island.
  • During preparations for a water landing, for undetermined reasons, the pilot did not identify the landing gear was in an unsafe condition. As a result, the aircraft landed with the right main wheels extended and then yawed to the right, nosed over and became submerged inverted.

Other factors that increased risk

  • The cautionary 'check gear' annunciation was very similar to the advisory annunciation for a normal water landing, increasing the risk that a pilot would not recognise that the landing gear was in an unsafe condition.
  • Following the impact, and with the aircraft submerged, the rear left door was unable to be opened by either the pilot or the passengers. As a result, the evacuation of the passengers was delayed.

Other findings

  • As required by the operator, the pilot had recently completed helicopter underwater escape training, which aided with their prompt underwater egress and subsequent rescue of the passengers from the inverted and submerged aircraft.
  • Push-out windows and door handles designed to expedite egress in an evacuation were available for retrofit on the DHC‑2 Beaver aircraft. VH‑OHU did not have either fitted and nor were they required to by regulation. 

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Safety action by Hamilton Island Air

Hamilton Island Air advised the following safety action was undertaken:

  • installation of a second mirror on the right wing of its current DHC‑2 aircraft
  • formal initial and refresher training on the pilot maintenance tasks
  • implementation of a daily washdown and preventative maintenance procedure checklist, which included a sign-off section to formally record when the activities were completed and by whom
  • implementation of a minimum weekly systems check flight, including landing gear cycle, where the aircraft had not been recently operated
  • implemented initial and annual theory ground school training, flight characteristics training and 180-day proficiency flight checks for all floatplane pilots, conducted by authorised flight training organisations.

Safety action by the Civil Aviation Safety Authority

Following review of the draft investigation report, the Civil Aviation Safety Authority advised it was intending to release airworthiness bulletin AWB 32-029 Issue 1 Supplementary Type Certificated Amphibian Float Main Gear Slide Wear in Marine Environments. Reflecting the information contained in the ATSB’s investigation report, the bulletin contains advice to operators and maintainers highlighting the importance of inspection and preventative maintenance aspects for retractable landing gear carriages fitted to amphibious aircraft when operated in a marine environment. The bulletin recommended that:

  • during scheduled maintenance of the landing gear, particular attention should be applied during a visual inspection for evidence of corrosion or mechanical damage to the hard anodized surface of the slide tubes
  • during periods of extended non-service, the landing gear slide tubes are lubricated and visually inspected for damage along their full length prior to the aircraft returning to service
  • during approved pilot maintenance. the main gear slide tubes are wiped clean and lubricated and the gear carriages are completely refreshed with clean grease. 

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilot and passengers of the accident flight
  • the operator and training pilots
  • the Civil Aviation Safety Authority
  • De Havilland Aircraft of Canada
  • Wipaire
  • the maintenance organisation for VH‑OHU
  • the maintenance facility that conducted the post-accident aircraft examination
  • Bureau of Meteorology
  • video footage from the accident flight and other photographs taken on the day of the accident.

References

Federal Aviation Administration. (2016). Human factors design standards. US Department of Transportation, United Sates Government.

Rice, E,V., & Greear, J.F. (1973). Underwater escape from helicopters. In Proceedings of the Eleventh Annual Symposium, Phoenix, AZ: Survival and Flight Equipment Association, 59-60. Cited in Brooks C. (1989) The Human Factors relating to escape and survival from helicopters ditching in water, AGRAD.

Salvendy, G., & Karwowski, W. (2021). Handbook of human factors and ergonomics (5th ed.). John Wiley & Sons, Inc, doi: 10.1002/9781119636113.

Yeh, M., Swider, C., Jin Jo, Y., & Donovan, C. (2016). Human factors considerations in the design and evaluation of flight deck displays and controls. Federal Aviation Administration, United States Government.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the pilot of the accident flight
  • the operator and training pilots
  • the maintainer of VH‑OHU
  • Civil Aviation Safety Authority
  • De Havilland Aircraft of Canada
  • Transportation Safety Board of Canada
  • Wipaire
  • United States National Transportation Safety Board.

Submissions were received from:

  • the operator
  • De Havilland Aircraft of Canada
  • Civil Aviation Safety Authority.

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

About ATSB reports

ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.

Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Constant wear lifejacket: an uninflated lifejacket worn about the person in a pouch or harness for the duration of the flight.

[2]     The GippsAero GA8 Airvan is a single piston-engine powered high-wing utility aircraft, with fixed tricycle landing gear that can seat up to 8 people, including the pilot.

[3]     CASA Schedule 5 was developed to provide ongoing airworthiness requirements for certain aircraft with inadequate maintenance schedules. Civil Aviation Order 100.5 General requirements in respect of maintenance of Australian aircraft provided a list of aircraft whose maintenance schedules are inadequate, and the CASA Schedule 5 procedures must be followed. This list included several De Havilland aircraft however, the DHC-2 was not on that list.

[4]     The maintenance records from prior to entry into Australia were not provided to the ATSB. In addition, advice from Wipaire indicated the colour of the anodising could vary and was not representative of the manufacture date.

[5]     PTFE, commonly known as Teflon™: polytetrafluoroethylene; the plastic produced by the polymerisation of tetrafluoroethylene, which has a low coefficient of friction and high resistance to temperature, chemicals, and radiation and is used for laboratory utensils, bearings, gaskets, non-stick lining for cookware, and as a waterproof fabric.

Occurrence summary

Investigation number AO-2024-055
Occurrence date 26/10/2024
Location Near Whitehaven Beach, Whitsunday Island
State Queensland
Report release date 10/11/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Incorrect configuration, Landing gear/indication
Occurrence class Accident
Highest injury level Minor

Aircraft details

Manufacturer De Havilland Canada/De Havilland Aircraft of Canada
Model DHC-2 (Beaver) MK I
Registration VH-OHU
Serial number 826
Aircraft operator Whitsunday Air Services Pty Ltd
Sector Piston
Operation type Part 135 Air transport operations - smaller aeroplanes
Departure point Hamilton Island Airport, Queensland
Destination Whitehaven Beach, Whitsunday Island, Queensland
Damage Substantial

Loss of control and collision with terrain involving Cessna 150L, VH-EYU, Bacchus Marsh aircraft landing area, Victoria, on 22 October 2024

Final report

Report release date: 10/07/2025

Investigation summary

What happened

On the morning of 22 October 2024, the pilot of a Cessna Aircraft Company 150L, registered VH‑EYU, was conducting a private flight from Bacchus Marsh aircraft landing area, Victoria. Strong and gusting winds were present. After commencing a take-off roll, the pilot rejected the take-off, before taxiing back to the same runway for a second take‑off.

On the second take-off, the aircraft became airborne and climbed to about 150 ft above the runway, before it pitched steeply nose-up, then the nose dropped suddenly, followed by the left wing dropping. The aircraft then entered a vertical descent, rotating approximately 270° before colliding with terrain. The pilot, who was the sole occupant of the aircraft, was fatally injured, and the aircraft was destroyed. 

What the ATSB found

The ATSB found that shortly after take-off, in strong and gusty wind conditions, the aircraft stalled at a height too low to recover before colliding with terrain. It is probable that the aircraft was too slow on take-off into those conditions, and that inputs made to counteract the crosswind increased the angle of attack of the left wing. These factors, combined with the wind conditions, increased the risk of a quick and unrecoverable stall.

Safety message

While an aerodynamic stall can occur at any airspeed, at any altitude, and with any engine power setting, it is most hazardous during take-off and landing when the aircraft is close to the ground. When gusting conditions are present, pilots should consider waiting for more benign conditions. Guidance advises pilots to conduct their own testing in progressively higher winds to determine both their own capability and that of the aircraft. 

Maintaining the aircraft’s attitude and correcting any change in attitude due to wind gusts during climb, is vital to ensure the critical angle of attack is not exceeded. Reducing the angle of attack by lowering the aircraft nose at the first indication of a stall is the most important immediate response for stall avoidance and recovery. 

Pilots must understand and recognise the conditions which make stall more likely and the symptoms of an approaching stall so they can act to prevent a stall before an unrecoverable condition develops. If pilots judge the weather to be suitable, they should consider climbing out at a higher airspeed to provide a buffer above their aircraft’s stall speed for detection and correction of an impending stall. 


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On the morning of 22 October 2024, at the Bacchus Marsh aircraft landing area (ALA), Victoria, a Cessna Aircraft Company 150L aircraft, registered VH‑EYU, was being prepared for a private flight under visual flight rules[1] to Lethbridge ALA, Victoria, about 35 km to the southwest. The weather conditions at the time were described as having strong, variable and gusty winds with a temperature of about 27°C.

Closed circuit television (CCTV) showed the pilot arriving for their flight at about 1000. Later, at about 1047, another CCTV camera located at a flying school, recorded the aircraft taxiing to the fuel bowser. After fuelling, the pilot drained a fuel sample from the aircraft fuel tanks and checked the sample. The pilot, who was the sole occupant, climbed in, then started the aircraft and taxied to a run‑up area[2] and performed engine run-up and flight control checks. They then taxied toward runway 27[3] for take‑off (Figure 1).

At about 1110 local time, a common traffic advisory frequency[4] (CTAF) recording captured the pilot stating that they were commencing their take‑off roll. Shortly after, the pilot transmitted another radio call stating that they were rejecting the take‑off. There was no further information provided by the pilot to explain why the take‑off was rejected. 

The rejected take-off attracted the attention of witnesses who were now observing VH‑EYU. The pilot taxied the aircraft off the runway and returned to the end of runway 27. At 1114, the pilot commenced a second take‑off roll.

The witnesses included a flight instructor. They identified that the aircraft appeared unstable after take-off. The CCTV showed the right wing dipping twice during this take‑off, with the pilot levelling the aircraft each time. The flight instructor stated that at about 50 ft, the aircraft pitched up quickly, before the nose was pushed down again.

After the aircraft had passed the runway intersection and reached an altitude of about 150 ft, it pitched steeply upward, before the nose and then the left wing rapidly dropped. The aircraft entered a nose down vertical descent to the left, rotating approximately 270° before colliding heavily with terrain. After the collision, personnel from the flying school attended the accident site and found the pilot fatally injured. The aircraft was destroyed. 

Figure 1: Bacchus Marsh ALA and VH‑EYU approximate flight path (yellow) and accident site

View of Bacchus Marsh ALA showing the runways and approximate flight path of VH-EYU and the accident site. Also shows the CCTV and its field of view, witness and windsock locations.

Source: Google Earth, annotated by the ATSB

Context

Pilot information

The pilot commenced their flight training in July 2019 and held a recreational pilot licence (aeroplane), which was issued on 14 November 2023. They held a single engine aeroplane class rating. The pilot also held navigation, controlled aerodrome, controlled airspace and flight radio endorsements which were issued on 19 April 2024. 

Overall, the pilot had accumulated about 184 hours total aeronautical experience, of which 71.9 hours were in the Cessna 152 and 3.8 hours in the Cessna 150.

The pilot joined Bacchus Marsh Aero Club on 19 August 2024 and had completed 3 club check flights with an independent instructor during September and October 2024. Since joining the club, the pilot had flown a total of 20.1 hours in Cessna 172, Cessna 152 and Cessna 150 aircraft. They had also flown 3.3 hours in a Cessna 152 the previous day. 

The pilot held a Class 2 aviation medical certificate issued by the Civil Aviation Safety Authority, without medical restrictions, which was valid until 19 March 2026.

Post-mortem examination 

The post-mortem and toxicology examinations did not identify any indication of incapacitation or substances that could have affected the pilot’s capacity to perform the flight.

Aircraft information

The Cessna 150L is a high wing, all-metal, 2‑place, single‑engine aircraft with a fixed tricycle landing gear. It is powered by a 4‑cylinder Teledyne‑Continental O‑200‑A engine, driving a 2‑blade fixed‑pitch propeller. VH‑EYU (Figure 2) was manufactured in the United States in 1974 and first registered in Australia in May 1974. It had been owned by the Bacchus Marsh Aero Club since December 2023. 

The aircraft was fitted with a stall warning horn on the left wing, which produces an audible signal to the pilot when the wing is approaching its critical angle of attack (AoA). The Cessna 150L’s stated stall speed in take‑off configuration with wings level was 48 kt.[5]

No crosswind limitation was published in the C150 L model owner’s manual. There was only a need for the manufacturer to demonstrate crosswind capability up to 8.5 kt (20% of the stall speed in a landing configuration). While it is possible that the aircraft may be capable of meeting the controllability standard in higher winds, this had not been established by the manufacturer.

Figure 2: VH-EYU

Photo of VH-EYU, provided by Bacchus Marsh Aero Club.

Source: Bacchus Marsh Aero Club

Recent maintenance history

The last 100‑hour periodic maintenance inspection was conducted on 19 January 2024. At the time of the accident, VH‑EYU had accrued a total time in service of 8,962.3 hours. Maintenance records also showed that since January, the following maintenance had been performed:

  • a 50-hour/6-month oil and filter change
  • the left brake was serviced
  • the flap position indicator spring was replaced.

The aircraft had flown about 36.3 hours since the last scheduled maintenance which was conducted on 21 April 2024. There were no open defects recorded on the maintenance release and no outstanding or overdue maintenance was noted. 

Aerodrome information

Bacchus Marsh aircraft landing area (ALA) was located about 6.5 km south of Bacchus Marsh, Victoria. It consisted of 2 sealed runways, 01/19 in a north‑south direction and 09/27 in the east‑west direction. The ALA was home to the Bacchus Marsh Aero Club, a pilot training school and several gliding clubs, as well as several privately owned aircraft. 

The ALA was in non‑controlled Class G airspace. Aircraft operating in the area did not require clearance and a common traffic advisory frequency (CTAF) was available for pilot‑to‑pilot communication. 

Bacchus Marsh Aero Club

Bacchus Marsh Aero Club operated several single-engine aircraft that were available to hire for approved club members, including the Cessna 150, 152, 172 and 182 models. Due to its status of being a private flying club and to satisfy insurance purposes, the club had a procedure in place for an independent flight instructor to conduct flight checks on new members prior to them being approved to fly club aircraft. 

Site information 

The accident site was in a barley field, 205 m south of the runway 27 centreline and to the west of runway 19/01 (Figure 1). The fuselage was orientated to the north. Ground impact marks were directly under the wreckage indicating no forward momentum. The damage signatures showed that the aircraft had impacted the field in a steep nose down attitude with the initial ground contact at the leading edge of the left wing. Severe disruption of the cockpit area, wing assembly and rear fuselage had occurred from the impact (Figure 3).

Figure 3: VH-EYU at the accident site

View of VH-EYU wreckage, highlighting the wing, fuselage and cockpit damage.

Source: ATSB

Wreckage examination

The ATSB’s examination of the wreckage did not identify any evidence of pre‑existing faults, flight control issues or engine issues and there was no evidence of birdstrike. 

All components were accounted for at the accident site. The right fuel tank had ruptured, while the left tank remained intact. A quantity of fuel was removed from the aircraft fuel tank for onsite testing and was found to be clean and clear of contaminants. Fuel was removed from the carburettor, which was also tested with no water or contaminants found.

The wings and centre fuselage roof section had separated and moved forwards as a result of the impact. Portions of the airframe were removed by first responders prior to ATSB examination, and these were photographed prior to removal. The stall warning horn on the left wing was damaged in the accident sequence and could not be tested for functionality. The flaps were noted to be retracted, which is the position required in the normal take‑off checklist. 

An examination of the seat rails showed that the pilot seat was locked into position and had not moved prior to the accident.

The engine and propeller displayed no pre‑existing damage. The engine was externally examined, and all components were accounted for. The engine was able to be rotated which indicated no significant internal damage had occurred. 

The propeller and flange had fractured from the engine crankshaft and there was evidence of rotation on the fracture surfaces. The propeller displayed minor rotational scoring and rearward bending which was indicative of low rotational energy at the time of impact. 

The throttle control in the cockpit was set at a low power position and had been bent upwards during the impact sequence. 

Survival aspects

The pilot had been wearing a lap/sash seat belt during the accident flight. The extent of the damage to the occupiable space of the aircraft cabin meant that the impact was not considered survivable.

Aircraft stall and spin behaviour 

Aerodynamic stalls

An aerodynamic stall is a rapid decrease in lift and increase in drag caused by the separation of airflow from the wing’s upper surface. A stall occurs when the angle of attack[6] exceeds the wing’s critical angle of attack,[7] resulting in the disruption to the smooth airflow over the wing. This can ordinarily occur at angles of around 16° (Figure 4). Due to the sudden reduction in lift from the wing and rearward movement of the centre of lift, an uncommanded nose‑down pitch ensues. 

The US Federal Aviation Administration (FAA) Airplane Flying Handbook (2021) states that:

• Impending Stall—an impending stall occurs when the AOA causes a stall warning but has not yet reached the critical AOA. Indications of an impending stall can include buffeting… or aural warning.

• Full Stall—a full stall occurs when the critical AOA is exceeded. Indications of a full stall are typically that an uncommanded nose down pitch cannot be readily arrested and may be accompanied by an uncommanded rolling motion... 

The FAA Airplane Flying Handbook (2021) also states that for an impending stall the pilot should:

…immediately reduce AOA once the stall warning device goes off, if installed, or recognizes other cues such as buffeting. The pilot should hold the nose down control input as required to eliminate the stall warning. Then level the wings maintain coordinated flight, and then apply whatever additional power is necessary to return to the desired flightpath.

Figure 4: Effect of increasing angle of attack leading to a stall condition

View of VH-EYU wreckage, highlighting the wing, fuselage and cockpit damage.

Source: CASA AvSafety, annotated by the ATSB

Aerodynamic spins

A spin can result when an aircraft simultaneously stalls and yaws.[8] The yaw can be initiated by rudder application (through manipulation of the rudder pedals) or by yaw effects from a range of factors that include aileron deflection, torque, wind and engine/propeller effects. A spin is characterised by the aircraft following a downward, corkscrew path and requires significantly more altitude for recovery compared to a wings level stall.

The spin recovery procedure stated in the Cessna 150L handbook was:

For recovery from an inadvertent or intentional spin, the following procedure should be used.

• retard the throttle to idle position

• apply full rudder opposite to the direction of rotation

• after one-fourth turn, move the control wheel forward of neutral in a brisk motion

• as rotation stops, neutralize rudder and make a smooth recovery from the resulting dive. 

Application of aileron in the direction of the spin will greatly increase the rotation rate and delay the recovery. Ailerons should be held in a neutral position throughout the spin and the recovery. Intentional spins with flaps extended are prohibited.

To recover from the spin, the pilot requires sufficient height to conduct the procedure and fly away. During the initial stages of a take‑off, there is insufficient height to perform these actions. 

Control input in a crosswind

In a crosswind, to prevent uncommanded roll, the pilot must turn the control yoke into wind. This will move the ailerons to change the relative angle of attack of each wing (Figure 5). The aileron on the into‑wind wing (right in this case) will move up, create a lower angle of attack and produce less lift. The aileron on the downwind wing (left in this case) will move down, creating a higher angle of attack and more lift. Therefore, resisting the rolling moment created by the crosswind.

Figure 5: Effect of aileron use on angle of attack

Figure shows how the camber of a wing changes with aileron deflection and the effect this has on angle of attack. The left wing shows the camber with neutral aileron. The middle wing represents the low wing in a turn and shows that as the aileron is deflected up, the camber of the wing decreases producing a lower angle of attack. The right wing represents the high wing in a turn and shows that as the aileron is deflected downwards, the camber of the wing increases producing a higher angle of attack.

Source: Flight Safety Australia

Guidance

The FAA Airplane Flying Handbook (2021) states for take‑off in gusty conditions that:

During take-offs in a strong, gusty wind, it is advisable that an extra margin of speed be obtained before the airplane is allowed to leave the ground. A take-off at the normal take-off speed may result in a lack of positive control, or a stall, when the airplane encounters a sudden lull in strong, gusty wind, or other turbulent air currents. In this case, the pilot should allow the airplane to stay on the ground longer to attain more speed, then make a smooth, positive rotation to leave the ground.

A Civil Aviation Safety Authority publication AC 91‑02 v1.2 – Suitable places to take‑off and land, and the FAA publication Personal minimums for wind both identify that is the responsibility of the pilot in command to consider the winds and determine if the aircraft can be operated safely in the prevailing conditions. The FAA publication advises pilots to conduct their own testing in progressively higher winds to determine both their own capability and that of the airframe.

Meteorological information

Forecast weather

The planned flight from Bacchus Marsh to Lethbridge was within the Victoria graphical area forecast (GAF)[9] region. The Bureau of Meteorology issued a GAF which included the Bacchus Marsh area, at 0900 on 22 October 2024, and was valid from 1000‍–‍1600. The forecast indicated visibility greater than 10 km and no cloud. A Grid Point Wind and Temperature Forecast was issued by the Bureau of Meteorology at 0525 on 22 October 2024. No wind and temperature was available in the Bacchus Marsh area below 5,000 ft. 

The Bureau of Meteorology issued aerodrome forecasts (TAF)[10] and meteorological aerodrome reports (METAR)[11] for Melbourne, Essendon, Avalon and Ballarat airports. A special meteorological report (SPECI)[12] was also issued, which highlighted that a significant wind gust had been recorded. 

There was no record that the pilot had used any personal login to access weather forecasts prior to their flight, from any official sources. It is unknown if the pilot had checked a forecast via other sources which did not require accounts for access.

Nearby airport weather

The actual weather at Bacchus Marsh ALA was not recorded and not available. However, forecasts and observation reports were available for nearby airports. Table 1 shows the recorded winds at Melbourne Airport leading up to the accident. Melbourne Airport is about 38 km on a bearing of 78° True (° T) from Bacchus Marsh. 

Table 1: Wind speed and direction recorded at Melbourne Airport

ReportTime (local)Bearing ° TWind speed (kt)Time before accident
METAR10000102274 minutes
SPECI100702021, gusting to 3267 minutes
METAR10300202044 minutes
METAR11000102014 minutes

Source: Bureau of Meteorology 

Table 2 shows the recorded winds at Ballarat Airport leading up to the accident. Ballarat Airport is about 59 km on a bearing of 293° T from Bacchus Marsh.

Table 2: Wind speed and direction recorded at Ballarat Airport

ReportTime (local)Bearing ° TWind speed (kt)Time before accident
METAR10003601374 minutes
METAR10303601344 minutes
METAR11003601014 minutes
METAR113036014-16 minutes

Source: Bureau of Meteorology 

Windsock indication

Figure 6 shows VH-EYU taxiing to the runway threshold in the opposite direction but parallel to the take‑off direction. The visible opening of the orange windsock in the background indicates headwind and crosswind components for take‑off.

Figure 6: VH-EYU taxiing prior to second take‑off

VH-EYU taxiing prior to second take-off with the gliding club windsock in the background showing the strong winds at the time.

Source: Supplied

Witness observations of the weather

A number of witnesses described the temperature to be ‘very hot’ (27°C) with strong and gusting winds at the time of the accident. The winds were changing in strength (15–30 kt) and direction (between runways 27 and 01) (Figure 7). A flight instructor, who was an eyewitness to the accident stated that they had cancelled a student’s flight which was to occur later in the day due to the gusty conditions. 

FlySto data from a Cessna 172

A Cessna 172 was flying nearby at the time of the accident and landed at Bacchus Marsh ALA 10 minutes after the accident. Data from the aircraft was uploaded to FlySto.[13] This data recorded the average wind from ground level up to 3,600 ft over a 40‑minute period. The wind direction varied between 262° T and 335° T and at speeds from 6–32 kt. At the time of the accident, this aircraft was located 14 km (8 NM) to the south of Bacchus Marsh ALA and had recorded a 27 kt wind from 290° T while on descent. The temperature recorded upon landing was 29°C.

A component of this data will be normal changes in wind speed and direction due to changes in altitude. For this reason, the average winds referenced in FlySto cannot be used to determine exact conditions at ground level at the time of the accident. 

Figure 7: Witness observation (red arc) and recorded data from FlySto (orange arc), showing approximate wind directions and speeds around time of VH‑EYU take‑off

Witness observation (red arc) and recorded data from FlySto (orange arc), showing approximate wind directions and speeds around time of VH-EYU take-off.

Source: Google Earth, annotated by the ATSB

CCTV and witness video

CCTV recorded the pilot’s arrival at the airport, refuelling, engine run‑up and control checks, and both take‑off runs. All videos showed evidence of strong and gusting winds creating movement in nearby trees and grass. Pitot cover flags on parked aircraft and clothing of people on the apron were observed flapping in the wind. The videos also captured wind noise varying with gusts.

A gliding club located to the east of the ALA had erected a small windsock, which was observed to be moving erratically with the varying wind strength and directions. The witness video provided, showed this windsock to be a smaller commercially available item. Due to its design, it did not meet the standards[14] for wind direction indicators and therefore was not able to provide any information of wind speed. 

Recorded information

CTAF recording

CTAF recordings provided the standard radio transmissions made by the pilot. The recordings also captured the engine sounds each time a transmission was made and showed that the engine sounded normal throughout the duration of the recordings. 

The pilot sounded calm during transmission and voiced no concern with the engine or aircraft after the first rejected take‑off and subsequent return for the second take‑off. 

Aircraft data

The aircraft was not equipped with either a cockpit voice recorder or a flight data recorder, nor was it required to be. Further, there was no active flight tracking equipment or other devices fitted to the aircraft to provide parameters from the accident flight. 

CCTV

The ATSB conducted frame‑by‑frame analysis of the CCTV of the second take‑off. This analysis showed that the groundspeed of the aircraft was 42 kt when the aircraft became airborne.

Related occurrences

AO-2014-023: Cessna 150G, VH-RXM, Loss of control during initial climb, 18 February 2014, Moorabbin Airport

An instructor and student pilot were conducting a trial instructional flight. The aircraft departed with a 3‍–‍4 kt tailwind. The student was operating the aileron and elevator controls, with the instructor operating the rudder. During the initial climb, the student continued to apply back pressure to the control column resulting in a reduction in optimal airspeed, and a higher‑than‑normal aircraft nose attitude. As the instructor attempted to rectify the aircraft’s profile, the right wing dropped, and the aircraft began to descend. 

The instructor’s efforts to recover the aircraft to a normal climb attitude were not successful, and the right side of the aircraft struck the ground. The aircraft bounced, then came to a halt on its left side. The instructor and student egressed through the right door, and both sustained minor injuries. The aircraft was substantially damaged.

NTSB Docket WPR21LA255 Cessna 150L, N1972L, Collision during take‑off, 30 June 2021, Mud Lake Airport (1U2), Terreton, Jefferson County, Idaho, United States

The pilot reported that, upon landing, they saw a crop duster aircraft descending for a short base for landing on the opposite runway. The pilot initiated a go around with the flaps still extended and with a high-density altitude. The aeroplane attained an altitude of about 50 to 100 ft above ground level when the aeroplane stalled, and the left wing dropped. The pilot attempted to recover but did not have enough height before the aeroplane collided with the ground. The aeroplane nosed over and came to rest inverted. The wings and fuselage were substantially damaged. The pilot and passenger sustained serious injuries.

Safety analysis

While there was no evidence that the pilot accessed official weather forecasts on the day of the accident, the pilot may have consulted informal sources, and they were able to experience the weather at Bacchus Marsh prior to departure. Through the movement of the distant windsock, vegetation, pitot covers on parked aircraft and the clothing of people in view of CCTV and video, it was evident that strong gusting winds were present. Noise on the audio track of CCTV also showed gusts were occurring. 

This supported observations of witnesses at the airfield of the conditions throughout the day and at the time of the accident. It is almost certain the wind conditions would have also been evident to the pilot at the time of take‑off. While no weather recording equipment was available at Bacchus Marsh, the evidence available allowed for an estimate of wind varying from west to north at speeds from around 10 kt gusting to 30 kt.  

There was no evidence of problems with the aircraft. The CCTV showed the pilot conducting pre‑take‑off run-up and control checks prior to the first take‑off. Witnesses and analysis of engine sound from CTAF broadcasts from VH‑EYU confirmed that the engine sounded normal. Additionally, post‑accident examination of the aircraft found no evidence of pre‑accident damage which would have affected the flight. 

There was no stated or discernible reason for the first rejected take‑off. The pilot gave no indication of an aircraft serviceability issue in their radio calls. They did not conduct any additional engine run‑up checks or stop the aircraft to perform any exterior airframe inspection. After exiting the runway, the aircraft was taxied without delay to runway 27 for the second take‑off.

On the second take‑off, CCTV analysis showed the groundspeed of the aircraft was 42 kt when the aircraft became airborne. Based on witness observation and the Cessna 150 measurements, the ATSB estimates the aircraft likely had an airspeed of over 50 kt, marginally faster than the 48 kt stall speed of the aircraft. At that time, crosswind was likely to be around 15 kt. 

Witnesses identified and CCTV footage showed that the aircraft’s attitude was unstable after becoming airborne. This indicates that the aircraft was affected by the strong, variable and gusting headwind and crosswind components as the pilot attempted the second take‑off. These uncommanded wind‑driven movements would require constant aircraft attitude adjustments by the pilot.

The flight instructor’s observation of the steep pitch‑up and controlled lowering of the nose which occurred at around 50 ft is consistent with the pilot manipulating the controls to avoid the aircraft descending back onto the runway and to maintain a suitable airspeed and take-off profile. The second uncorrected steep pitch‑up which occurred at around 150 ft, and the subsequent dropping of the left wing and nose resulting in entry into a left incipient spin, was consistent with a fully developed stall and loss of control in flight. This, in turn, was consistent with evidence of the accident site, in which the aircraft wreckage was confined to a small area, with evidence of a high vertical impact and low forward speed. 

In this accident, it is almost certain that, after take‑off and at low level, the aircraft was subjected to a strong and gusting wind. The nature of the prevailing winds increased the likelihood of a drop in airspeed during a phase of flight where the aircraft was flown at a high angle of attack, leading to an impending stall condition. 

It is possible that the impending stall period was very short due to gust strength and the pitch‑up movement created conditions for aerodynamic stall. Further, as the airspeed at take‑off was likely only a few knots higher than the stall speed, there was minimal buffer to account for any sudden drop of wind strength. The evidence indicates that the angle of attack of the wings increased beyond the critical angle, the left wing of the aircraft aerodynamically stalled, and the aircraft entered the incipient phase of a spin. The stalling of the left wing indicates that the angle of attack on the left wing was higher than that on the right. This is likely due to control inputs to counteract a crosswind from the right.

The actions that take place when the aircraft enters a spin require the pilot to retard the throttle. The throttle position in the aircraft was found in a low power setting, which was likely due to the pilot responding to the aircraft entering the incipient phase of a spin. Because the aircraft stalled at a height of about 150 ft, there was insufficient height to recover before the aircraft collided with terrain. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following finding is made with respect to the loss of control and collision with terrain involving Cessna 150L, VH-EYU, at Bacchus Marsh aircraft landing area, Victoria, on 22 October 2024. 

Contributing factors

  • It is probable that the aircraft was too slow on take‑off for the strong and gusty wind conditions and significant crosswind, meaning there was minimal buffer to manage an impending stall.  Shortly after take‑off, the aircraft stalled at a height too low to recover, resulting in a collision with terrain. 

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • Bacchus Marsh Aero Club
  • Civil Aviation Safety Authority
  • Victoria Police
  • the maintenance organisation for VH-EYU
  • Airservices Australia
  • Bureau of Meteorology
  • Peninsula Aero Club
  • Oxford Aviation Academy
  • TVSA Pilot Training
  • witnesses
  • video footage of the accident flight and other videos taken on the day of the accident
  • recorded CTAF communications. 

References

Civil Aviation Safety Authority 2019, Strong and gusty winds, Civil Aviation Safety Authority, Canberra, ACT Strong and gusty winds | Flight Safety Australia
Civil Aviation Safety Authority 2020, Advisory Circular AC 61-16v1.0, Civil Aviation Safety Authority, Canberra, ACT, https://www.casa.gov.au/spin-avoidance-and-stall-recovery-training

Civil Aviation Safety Authority 2020, Part 139 (Aerodromes) Manual of Standards 2019, Civil Aviation Safety Authority, Canberra, ACT, Part139_(Aerodrome)_MOS.pdf pp 196-198.

Civil Aviation Safety Authority 2019, Rudder, ailerons, stalls and spins, Civil Aviation Safety Authority, Canberra, ACT Rudder, ailerons, stalls and spins | Flight Safety Australia
Civil Aviation Safety Authority 2022, Stalls in the circuit, Civil Aviation Safety Authority, Canberra, ACT Stalls in the circuit | Flight Safety Australia 

Civil Aviation Safety Authority 2022, Advisory Circular AC 91-02v1.2, Civil Aviation Safety Authority, Canberra, ACT https://www.casa.gov.au/guidelines-aeroplanes-mtow-not-exceeding-5-700-kg-suitable-places-take-and-land pp21-22.

Civil Aviation Safety Authority 2024, AvSafety: Preventing a stall at low level, Civil Aviation Safety Authority, Canberra, ACT, Preventing a stall at low level

Federal Aviation Administration 2021, Airplane Flying Handbook (FAA-H-8083-3C), Federal Aviation Administration, Washington DC Airplane Flying Handbook 

National Transportation Safety Board 2015, NTSB Safety Alert 19 / Prevent Aerodynamic Stalls at Low Altitude, National Transportation Safety Board, Washington DC NTSB Safety Alert 19 / Prevent Aerodynamic Stalls at Low Altitude

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the Civil Aviation Safety Authority
  • the Bacchus Marsh Aero Club
  • the National Transportation Safety Board.

Any submissions from those parties were reviewed and, where considered appropriate, the text of the draft report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]      Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to allow the pilot to see where the aircraft is going.

[2]      Run-up area: a designated area of an airfield where pilots can perform functional pre-flight checks of aircraft systems.

[3]      Runway number: the number represents the magnetic heading of the runway. In this case, ‘27’ represents a magnetic heading of 270°.

[4]      Common traffic advisory frequency (CTAF): radio frequency on which pilots monitor and use to make positional broadcasts when operating within a 10 NM radius of the airport.

[5]      The Cessna 150L Owner’s Manual lists all speeds in miles per hour. 

[6]      Angle of attack: the acute angle between the chord line of the airfoil and the direction of the relative wind.

[7]      Critical angle of attack. the angle of attack at which a wing stalls regardless of airspeed, flight attitude, or weight.

[8]      Yaw: the motion of an aircraft about its vertical or normal axis.

[9]      Graphical Area Forecast (GAF): provides information on weather, cloud, visibility, icing, turbulence and freezing level in a graphical layout with supporting text.

[10]    Aerodrome Forecast (TAF): a statement of meteorological conditions expected for the specified period of time in the airspace within 5 nautical miles (9 km) of the aerodrome reference point.

[11]    METAR (Meteorological Aerodrome Report) is a routine aerodrome weather report issued at half hourly time intervals. The report ordinarily covers an area of 8 km radius from the aerodrome reference point.

[12]    SPECI: a special report of meteorological conditions, issued when one or more elements meet specified criteria significant to aviation.

[13]    FlySto is a web-based application that allows for upload and interpretation of flight data from a range of avionics devices.

[14]    The standards for windsocks are outlined in Part 139 Aerodrome Manual of Standards, which provides information for windsocks and their interpretation.

Preliminary report

Report release date: 16/12/2024

This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003. 

The occurrence

On 22 October 2024, at about 1110 local time, the pilot of a Cessna 150L registered VH‑EYU, commenced the take-off roll on runway 27[1] at Bacchus Marsh airfield, Victoria (Figure 1). Shortly after, the pilot made a radio call stating that they were rejecting the take‑off. The aircraft was then taxied off the runway and returned to the threshold of runway 27, where at 1114 the pilot recommenced the take-off.

Several witnesses at the airfield observed the second take-off and identified that, during its initial climb, the aircraft attitude pitched steeply upward. Witnesses described that the left wing dropped rapidly. The aircraft then entered a vertical descent, rotating approximately 270° before colliding heavily with terrain. The pilot (who was the sole occupant) sustained fatal injuries and the aircraft was destroyed. There was no post-impact fire. 

Figure 1: Bacchus Marsh airfield and VH-EYU accident location

Figure 1: Bacchus Marsh airfield and VH-EYU accident location

Source: Google Earth, annotated by the ATSB

Context

Pilot information

The pilot held a Recreational Pilot Licence (Aeroplane) and a Class 2 Aviation Medical Certificate, valid until March 2026. The pilot held a single engine aeroplane rating, and navigation endorsement. At the time of the accident, the pilot had about 184 hours total aeronautical experience, of which 3.8 hours were in Cessna 150 aircraft. 

Aircraft information

The Cessna 150L is a high wing, all-metal, 2-place, single-engine aircraft with a fixed tricycle landing gear. It is powered by a 4-cylinder Teledyne-Continental O-200-A engine, driving a 2-blade fixed-pitch propeller. The aircraft was manufactured by Cessna in the United States in 1974 and first registered in Australia in May 1974. It had been owned by the Bacchus Marsh Aero Club since December 2023 (Figure 2).

The last 100-hour periodic maintenance inspection was conducted on 19 January 2024. At the time of the accident, it had accrued a total time in service of 8,962.3 hours. The aircraft had flown about 34 hours since the last scheduled maintenance which was conducted on 21 April 2024. There no known defects documented on the aircraft maintenance release.

Figure 2: VH-EYU

Figure 2: VH-EYU

Source: Bacchus Marsh Aero Club

Aerodrome information

Bacchus Marsh airfield is located about 6.5 km south of Bacchus Marsh, Victoria, Australia. It is an aircraft landing area (ALA) consisting of 2 sealed north/south (01/19) and east/west (09/27) runways. The airfield was primarily used by the Bacchus Marsh Aero Club, a pilot training school and several gliding clubs. 

Bacchus Marsh Aero Club

Bacchus Marsh Aero Club operates several high wing single-engine aircraft available to hire for approved club members, including the Cessna 150, 152, 172 and 182. The pilot joined the club on 19 August 2024 and subsequently completed check rides with an instructor on 13 September, 27 September and 4 October 2024.

Site information 

ATSB investigators first attended the accident site on 23 October 2024. The aircraft had impacted into a barley field 205 m south of the runway 27 centreline and was orientated toward the north. The damage signatures confirmed that it had impacted the field in a steep nose down attitude. Severe disruption of the cockpit area, the wing assembly and rear fuselage had occurred from the impact (Figure 3).

Figure 3: VH-EYU at the accident site near to the airfield runways

Figure 3: VH-EYU at the accident site near to the airfield runways

Source: ATSB

Wreckage examination

The ATSB conducted a preliminary examination of the aircraft wreckage in the field, then moved the wreckage to a secure hangar for detailed examination. The examinations identified:

  • no evidence of pre-impact defects with the flight controls or structure
  • all components were accounted for at the accident site
  • the engine was able to be rotated and there were no obvious defects upon external examination
  • the throttle setting was at idle position (low power)
  • rotational damage signatures to the propeller were minimal which indicated a low engine power setting at the time of the impact
  • the propeller and flange had fractured from the engine crankshaft.

A quantity of fuel was removed from the aircraft for onsite testing and was found to be clean and clear of contaminants. 

Meteorological information

Forecast

The Bureau of Meteorology (BoM) issued a graphical area forecast that included the Bacchus Marsh area, at 0900 on 22 October 2024, that was valid from 1000–1600. The forecast indicated visibility greater than 10 km and no cloud. 

Witness observations of the weather

Witnesses at Bacchus Marsh airfield described the wind at the time of the accident as strong and gusty, changing in direction and strength. A flight instructor stated that they had cancelled a student’s flight due to the increasingly gusty conditions which were present on the day. 

Meteorological observations 

There was no BoM aerodrome weather information specifically for Bacchus Marsh, but the ATSB obtained meteorological observations for the surrounding areas of Melbourne, Essendon, Avalon and Ballarat airports (Figure 4).

Figure 4: Location of Bacchus Marsh airfield relative to nearby aerodrome weather forecast locations

Figure 4: Location of Bacchus Marsh airfield relative to nearby aerodrome weather forecast locations

Source: Google Earth, annotated by the ATSB

Table 1 shows the recorded winds in meteorological aerodrome reports (METAR)[2] and special meteorological reports (SPECI)[3] issued between 1000 and 1200 on 22 October 2024. The wind direction is in degrees true[4] rounded to the nearest 10 degrees. The wind direction and speed are the mean values over 10 minutes, and the gust is the maximum wind speed over a 2-minute period.

Table 1: Aerodrome wind observations

TimeMelbourneEssendonAvalonBallarat
1000010° 22 kt360° 15 kt020° 8 kt360° 13 kt
1007[1]020° 21 kt gusting to 32 kt   
1020[1] 360° 17 kt gusting to 27 kt  
1030020° 20 kt360° 16 kt360° 10 kt360° 13 kt
1100010° 20 kt360° 18 kt330° 12 kt360° 10 kt
1130010° 19 kt360° 15 kt350° 12 kt360° 14 kt
1200010° 17 kt360° 15 kt350° 11 kt360° 16 kt

[1] SPECI

Further investigation

To date, the ATSB has:

  • examined the aircraft wreckage
  • conducted witness interviews
  • reviewed common traffic advisory frequency recordings
  • reviewed CCTV footage and mobile phone footage
  • obtained weather information.

The investigation is continuing and will include:

  • further review of the pilot’s experience, qualifications and training
  • further review and analysis of recorded CCTV and mobile phone footage
  • further analysis of the weather conditions
  • examination of the aircraft maintenance history.

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken. 

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2024

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Runway number: the number represents the magnetic heading of the runway. In this case, 27 represents a magnetic heading of 270°.

[2]     METAR: a routine aerodrome weather report issued at half hourly time intervals.

[3]     SPECI: a special aerodrome weather report issued only when meteorological parameters meet specific criteria.

[4]     The magnetic variation at Bacchus Marsh was 11° east.

Occurrence summary

Investigation number AO-2024-053
Occurrence date 22/10/2024
Location Bacchus Marsh aircraft landing area
State Victoria
Report release date 10/07/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Loss of control
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Cessna Aircraft Company
Model 150L
Registration VH-EYU
Serial number 15075559
Aircraft operator Bacchus Marsh Aero Club
Sector Piston
Operation type Part 91 General operating and flight rules
Departure point Bacchus Marsh, Victoria
Destination Bacchus Marsh, Victoria
Damage Destroyed

Collision with terrain during go-around involving Cessna U206F, VH-TDQ, 39 km south-east of Moora, Western Australia, on 1 September 2024

Final report

Report release date: 30/06/2025

Investigation summary

What happened

On the morning of 1 September 2024, the pilot of a Cessna U206F, registered VH-TDQ and operated by Fly Esperance, departed a private aircraft landing area 21 NM (39 km) southeast of Moora, Western Australia (WA) with 5 passengers onboard for a 15-minute local area flight. On return to the landing area, the aircraft bounced twice on landing before the pilot attempted a go‑around. During the go-around, the pilot incorrectly set the flap, and the aircraft lost height impacting its right wing with terrain, resulting in minor damage. The aircraft then touched down on the landing gear in a field adjacent to the runway. 

The pilot then evacuated the passengers. The front seat and middle row passengers egressed through the pilot’s forward left cabin door. The pilot then proceeded to assist the egress of 2 passengers seated in the rear seat row of the aircraft through the right-side cargo door emergency exit. The aircraft’s flaps remained extended in the 10° position which blocked the forward half of the cargo door emergency exit. The pilot was unable to retract the flaps and the passengers, an older person and child, were then forced to climb over the middle row of seats and egress through the pilot’s forward left cabin door. None of the occupants reported injuries.

What the ATSB found

On return to the aircraft landing area, the pilot conducted a non-standard approach to join the circuit. This reduced the time available for the pilot to configure the aircraft, manage the airspeed and prepare for a short field landing. 

As a result of excess speed on approach for a full flap, short field landing, the aircraft landed long and bounced twice, at which point the pilot elected to conduct a go-around. As the aircraft began to climb away, the pilot retracted the flap further than intended and as a result, the aircraft could not achieve adequate climb performance.

The rear emergency exit was the double cargo doors, which required the forward half of the door to be opened before the rear door could be opened. With the flaps extended in the 10° position when the aircraft came to rest, the full opening of the forward cargo door was not possible. The forward door could still be made ajar with the flaps extended, enough to reach and operate the rear door handle. However, the rear seat passengers were not fully aware how to do this and were unable to open the rear cargo door to enable an emergency exit.

The pilot attempted to assist the rear seat passengers’ egress from outside the aircraft, however they were unaware that the rear cargo door on the Cessna 206 could be opened from the outside when the front cargo door was blocked by the extended flaps. After the pilot unsuccessfully attempted to retract the flaps, they instructed the passengers to climb over the middle row seats to egress via the pilot’s forward left cabin door.

The ATSB found that the operator’s pre-flight passenger briefing did not include the demonstration of, and pilots were not trained how to operate, the emergency exit via the cargo door with the flaps extended. 

Similar to previous ATSB and international investigations involving Cessna 206 accidents requiring emergency egress, it was found that without the installation of optional cargo door modifications or a reduction in passenger seats, the emergency egress of rear seat passengers was impeded when the flaps are extended. The difficulty in egressing via the cargo door emergency exit (when flaps were extended) increases risk to passenger survivability in the event of a post-accident fire or water ditching. This has been formally recognised in Canada where cargo door modifications are compulsory unless middle row passenger seating is reduced. However, this is not the case in the United States, where the Cessna 206 was certified, nor in Australia. 

What has been done as a result

To advise Cessna 206 pilots and operators of the difficulties occupants have encountered egressing the rear cargo door as identified in several transport safety investigations, the ATSB issued safety advisory notice (AO-2024-049-SAN-001). The safety advisory notice encourages pilots and operators to ensure a thorough pre-flight passenger demonstration is conducted of the rear cargo emergency exit egress when the wing flap remains extended.

Fly Esperance Pty Ltd also advised that a staff training exercise had been conducted to demonstrate the process for operating the rear door in the event of post-landing flap extension and has advised that this procedure is to be emphasised on all pre-departure passenger briefings. The ATSB will monitor this safety action until the adoption of procedural changes to staff training and operational pre-flight safety briefings.

Furthermore, a second safety advisory notice was issued to strongly encourage operators and owners to review Transport Canada Airworthiness Directive CF-2020-10, and consider either the removal of a middle row seat to improve rear seat occupants’ access to the pilot’s forward left cabin door or the fitment of approved Cessna 206 emergency exit modifications to reduce the risk created by the extended flap preventing the immediate and unobstructed use of the rear cargo doors during an emergency exit.

Fly Esperance Pty Ltd advised it is in the process of investigating the various STCs mentioned in the report, to see which will be best suited to VH-TDQ in order to improve egress from the aircraft in the event of flaps being deployed.

After the occurrence, the operator conducted an internal review and has made the following amendments to the company operations manual:

  • Added pictorial for non-controlled aerodrome circuit procedure to clarify the joining procedure at non-controlled aerodromes.
  • To assist pilots to identify a stable approach an aircraft landing weight table has been added, indicating the recommended speeds for landing with aircraft flaps retracted and extended.
  • Company aircraft will now have portable GPS tracking devices improving the visibility of the aircraft when away from base.
  • The operator also reported that a greater emphasis will be placed on pilots-in-command under supervision training prior to a company line check, highlighting what can happen when standard procedures are not followed.

The operator advised that its updated operations manual had been provided to CASA for approval. 

Safety message

This occurrence further demonstrates the difficulty occupants of the Cessna 206 face during an emergency egress via the cargo door, when the wing flaps remain extended. This highlights the importance of Cessna 206 pre-flight passenger briefings incorporating a demonstration of the limitations of the cargo door as an emergency exit with the flaps extended.

Furthermore, owners and operators of Cessna 206 aircraft are encouraged to review and assess changes to the aircraft passenger configuration implemented by Transport Canada with Airworthiness Directive CF-2020-10. As an alternative, several acceptable means of compliance for the Airworthiness Directive exist, providing modifications to the emergency exits of the aircraft and thereby improving the survivability in the event of an incident or accident.

Summary video


The occurrence 

The day before the accident

On 31 August 2024, the pilot of a Cessna U206F, registered VH-TDQ and operated by Fly Esperance, departed Esperance Airport, Western Australia (WA). The aircraft was ferried to a private aircraft landing area (ALA), 50 NM (93 km) north‑west of Esperance to conduct a non‑scheduled air transport flight to a private ALA about 21 NM (39 km) south‑east of Moora. The 3 passengers and pilot would spend the night at the property with the intention of returning the following day. 

On the first arrival at the destination ALA, the pilot made an approach to the westerly runway and configured the aircraft with 20° flap[1] for landing. During the first landing attempt, the aircraft bounced and the pilot conducted a go-around.[2] On the second landing attempt, the pilot configured the aircraft in a 40° full-flap configuration and landed without incident.

Accident flight

On the morning of 1 September 2024, the customers requested two 15-minute local flights for the family members they had been visiting. The pilot consulted the operator’s chief pilot by phone who approved the flights. The pilot then collected the passenger’s weights and assigned them to each flight.

The pilot gathered the passengers of both flights together and conducted a group safety briefing before the passengers on the first flight boarded the aircraft. With 5 passengers on board, the pilot took off on the western runway and departed about 1050 local time, tracked to the north before returning to the ALA a short time later (Figure 1). About 2 NM (3.7 km) north and within sight of the ALA, the pilot assessed that the aircraft was too high and conducted a left orbit to reduce height. 

The pilot reported they were advised the previous day by the local agricultural pilots to utilise the uphill slope for landing using the easterly runway and recalled, as there were no other aircraft in the vicinity, directly joining the base leg of the circuit for the easterly runway. They observed a 75 kt airspeed on final approach before configuring the aircraft for a full flap final approach for landing.

Figure 1: VH-TDQ flight track 

Google Earth image of VH-TDQ flight path. Marked is the ALA, left hand orbit and height when the aircraft joins a base leg and speed on final approach

Source: Google Earth, annotated by the ATSB

The pilot landed the aircraft about 80 m (Figure 2) past the end of the easterly runway and bounced twice before they applied full power and commenced a go-around. The pilot was unable to recall their airspeed at the time of the flap reduction, however reported that the aircraft had probably dissipated a considerable amount of speed during the bounces prior to initiating a go‑around. As the aircraft began the initial climb the pilot reduced the flap setting, unknowingly mis-selecting the 10° setting.

Figure 2: Aircraft landing area

Airfield and flight path from the go-around of VH-TDQ. Insert within the images is a still capture of video showing the aircraft landing abeam the nearby gravel road.

Source: Google Earth, annotated by the ATSB

As the flap retracted, the aircraft lost height and the pilot was unable to maintain control. The aircraft dropped the right wing and the right wingtip grazed the ground in the adjacent field. 

The right wingtip then raised above the crop height, however the propeller and landing gear remained partially in the crop (Figure 3) increasing drag and reducing speed. Shortly after, the aircraft touched down on its landing gear with the propeller making full contact with the crop and stopping the engine. The aircraft came to a stop upright, about 250 m from the runway, with the flaps extended in the 10° position. The pilot recalled at this point they switched off the aircraft’s fuel and electrics.

Figure 3: Aircraft landing gear marks in field adjacent to the runway

Marked is the location of the right wing tip dislodged during the impact with the ground.

Source: Fly WA Group, annotated by the ATSB

The pilot then checked on the welfare of the passengers and as a precaution, instructed them to evacuate the aircraft.

The pilot successfully egressed the front seat and middle-row passengers through the forward left cabin door. They then proceeded to the right side of the aircraft to assist the 2 passengers in the rear seats egress through the right-side cargo doors. 

On approaching the rear of the aircraft, the pilot observed that the extended flap had blocked the forward half of the cargo door and therefore believed they would not be able to open the rear half of the cargo emergency exit. After an unsuccessful attempt to retract the flaps, the pilot reported they were no longer operational. They did not attempt to open the rear cargo door further and instructed the rear seat passengers, an older person and young child, to egress over the middle row seat and then through the pilot’s forward left cabin door. 

The aircraft received minor damage to the right fibreglass wingtip and aileron. No injuries were reported, and all passengers successfully evacuated the aircraft. 

Context

Pilot information

The pilot held a commercial pilot licence (aeroplane), issued in August 2016. At the time of the accident, the pilot had about 390 hours of total flying experience, with 134.4 hours as pilot in command and about 30 hours on the Cessna 206. The pilot had operated for 49.4 hours in the last 90 days and held a current class 1 medical certificate that was valid until 29 July 2025.

The pilot was employed by the operator in June 2024 and had flown scenic flights from Jandakot, Western Australia (WA), before gaining full time employment with the same operator to conduct flights from the operator’s Esperance base, where the pilot had been located since August 2024.

During their initial employment with the operator, the pilot received about 13 hours of line training. The training included: 

  • emergency procedures
  • remote airfields
  • short fields
  • maximum all-up weight flight. 

The pilot’s logbook indicated a check flight was conducted by the operator’s chief pilot on 19 July 2024. They then began commercial flights for the operator about 1 week later. 

Although they had held a commercial licence since 2016, this was the pilot’s first aviation employment, having completed training and private flying before gaining employment with the operator. The logbook also indicated that prior to the pilot’s employment with the operator, limited flying was conducted, with a total of 4.2 hours flown in the 12 months before commencing with the operator.

Aircraft information

General information

The Cessna U206F is a single piston engine, high winged, 6-seat, unpressurised aircraft with fixed landing gear. The aircraft was powered by a Teledyne Continental IO-520 engine. 

VH-TDQ was manufactured in the United States in 1975 and first registered in Australia in August 1975. Fly Esperance became the registration holder on 29 April 2023. 

Cessna 206 variants

The Cessna 206 was produced between 1963 and 1986. In 1998, Cessna restarted production of the Cessna 206 and the aircraft remains in production.

The original model, named the Cessna 206 Super Skywagon, was produced between 1963 and 1965 and featured the rear right side double cargo doors. Subsequent models (Table 1) were also manufactured with the double cargo doors and included numerous different models between 1963 and 1986. Cessna aircraft company halted production of 206 aircraft between 1987 and 1997. Production resumed in 1998 with the current model 206H.

Table 1: Cessna 206 models manufactured with the double cargo doors

YearCessna 206 model name
1963/65206 Super Skywagon
1966*U206A 206 Super Skywagon
1967*U206B Super Skywagon
1968*U206C Super Skywagon
1969*U206D Super Skywagon
1970/71*U206E Skywagon 206/Stationair
1972-76*U206F Stationair
1977-86*U206G Stationair
1998-current*206H Stationair

* Indicates model was also manufactured with a turbo variation

Aircraft flaps

The Cessna 206 has an electrically‑controlled flap system. This requires the battery master[3] to be on and also requires the cargo doors to be completely closed. Closed cargo doors trigger a micro‑switch, located in the doorframe, which completes the electrical circuit and then allows flap movement. As the Cessna 206 flaps extend across the closed forward cargo door (see Cabin layout and exits), this provides a protection so the flaps cannot be inadvertantly extended into an open cargo door and damage the aircraft. 

The flap control lever in the Cessna U206F is located on the pilot’s right side (Figure 4) and is clearly visible from the pilot’s seat. The lever allows the flaps to be set in any position between 0° (flaps fully retracted) and 40° (full-flap extension) with an adjacent placard marking the flap position. 

The pilot described on numerous occasions during an interview with the ATSB ‘hitting or flicking’ the flap selector lever, identifying that the flap selection was sometimes made without the time taken to confirm the flap selection was in the correct position. 

The operator’s chief pilot reported they had not observed the pilot manipulating the lever like this during the 13 hours of in command under supervision (ICUS) flying they completed with the pilot.

Figure 4: Cessna U206F cockpit

Cessna U206 F cockpit with an insert of the flap control lever indicating the fully retracted flap position and full flap position of the lever.

Source: Pilot, annotated by the ATSB

Cabin layout and exits

VH-TDQ was operated in a 6-person configuration with 2 front row (pilot) seats, 2 middle row seats and 2 rear seats (Figure 5).

Figure 5: Cessna 206 standard cabin seating configuration 

Profile view of the standard cabin configuration for the Cessna 206

Source: TSB investigation report A18W0129, adapted by ATSB to match occurrence aircraft 

VH-TDQ included 2 emergency exits, the pilot’s forward left cabin door and a double ‘clam shell’ style cargo door located at the rear right of the aircraft cabin. Passengers seated in the middle row seats are able to access the pilot’s forward left door when the pilot’s seat is moved into a forward position. The forward part of the cargo door overlaps the rear cargo door as a preventative measure to stop the rear door (rear hinged) from opening in flight and damaging the aircraft. The rear cargo door cannot be opened independently of the front cargo door.

Wing flap extension greater than 10° results in the flap blocking the forward part of the cargo door (Figure 6) and restricts the opening to about 8 cm. When the aircraft wing flaps remain extended, the forward cargo door must be opened as far as possible to then allow the rear door to be opened. Further detail is discussed below in Cessna 206 rear passenger emergency egress.

Figure 6: Cessna 206H showing extended flap blocking forward cargo door

Cargo door with flap extended to the 40 degree position clearly blocking the forward cargo door from opening.

Source: ATSB

Meteorological information

The pilot reported that they assessed the local weather conditions via their NAIPS[4] account on the morning of the occurrence flight and recalled that the predicted wind at the aircraft landing area (ALA) was calm.

Bureau of Meteorology data from the nearest recorded locations at the time of the occurrence indicated local winds between 12–14 kt in a south-westerly direction (Figure 7).

Figure 7: Weather reporting locations in relation to the private aircraft landing area

Google Earth image marking the nearest weather reporting stations to the ALA. Insert table shows locations recorded wind from the south-west between 7 and 14 kt.

Source: Google Earth, annotated by the ATSB

Aeroplane landing area information

The ALA was on privately‑owned farming land and was regularly used by agricultural pilots to conduct spraying of crops in the local area. The elevation of the ALA was about 800 ft above mean sea level (AMSL) and the runway orientation was about 120/300°[5] and had a gradual slope that increased towards the east, rising about 40 ft over the length of the runway. It was surrounded by waist-high crops, had a gravel surface and a useable length of about 570 m. The ALA did not have a windsock, nor was there a wind indicating device located nearby.

Prior to operating at the ALA, the operator spoke with the landowners to gain understanding of the recent landing area conditions, as they had not flown to the location previously. They were put in contact with the agricultural pilots who had been recently operating from the field and received a landing area condition report. The operator assessed that the area was suitable for the Cessna 206.

Standard circuit pattern

A circuit is the specified path to be flown by aircraft operating in the vicinity of an aerodrome (Figure 8). It comprises of upwind, crosswind, downwind, base and final approach legs.

Figure 8: Standard left-hand circuit pattern

Image depicts left hand circuit pattern from runway 09

Source: SKYbrary, modified by the ATSB

The Civil Aviation Safety Authority (CASA) Advisory Circular AC 91-10v1.3 advised pilots that joining a base leg of a circuit is not a standard procedure. Stating:

CASA recommends that pilots join the circuit on either the crosswind (midfield) or downwind leg. However, pilots who choose to join on base leg should only do so if they have familiarised themselves with the weather conditions to be expected and aerodrome serviceability.

The AC advised that pilots who join the base leg of the circuit increase the risk of a downwind landing and may conflict with other traffic using the into-wind runway. It also stated that late go‑around decisions and landings on a closed runway were more common.

Recorded data

Flight Radar 24 data[6] indicated that when the pilot commenced the left-hand orbit approaching the ALA, that the aircraft was about 2,000 ft AMSL and at the conclusion of the orbit, as the aircraft joined the base leg, it remained at about 2,000 ft AMSL, about 1,200 ft above the ALA. As the aircraft became established on final approach for the easterly runway, the aircraft height was recorded as 1,500 ft AMSL, 700 ft above the ALA and 1.6 NM from the runway threshold.

Flight Radar 24 showed that the aircraft’s ground speed had slowed to around 75 kt on the base leg of the approach to landing. As the aircraft turned onto final approach the ground speed increased, reaching 92 kt and indicated about 85 kt ground speed at the last data recording on short final for the easterly runway.

Video footage from a passenger seated in the rear left seat was obtained by the ATSB. Video footage showed that the initial touchdown point (Figure 2) was about 80 m past the runway threshold, reducing the remaining runway length to about 490 m. The footage also showed that during the go-round, the aircraft began to lose height shortly after the flaps were retracted and that this was followed by a roll to the right.

Operator’s internal review

On the day of the accident, the operator’s chief pilot attended the accident site, gathered images, reviewed the aircraft damage and debriefed with the pilot.

The chief pilot advised that post‑accident aircraft testing was carried out later that day and the flaps were tested and found to be operational.

From the pilot’s report, flight data and images gathered, the operator completed a detailed internal review of the accident. A summary of the findings included:

• the aircraft’s approach became unstable due to the excess speed

• the speed was more appropriate for a 20° flap setting

• the excess speed likely resulted in the aircraft ‘floating’ and landing long on the runway

• after an initial bounce on landing the pilot continued the approach to land before a second bounce

• inadvertent incorrect flap setting reduced the aircraft climb performance.

Cessna 206 procedures

Unstable approach procedure

The Cessna 206F aircraft flight manual (AFM) advised pilots that the approach speed for a full‑flap, short field landing should be 75 mph (65 kt).

The operator’s exposition stated that the airspeed for the stabilised approach criteria below 1,000 ft is not more than VREF[7] (65 kt) + 5 kt.

Data from Flight Radar 24 showed the aircraft ground speed had slowed to 75 kt on the base leg of the circuit, before increasing to 92 kt ground speed on final approach. The pilot reported the airspeed on final was 75 kt prior to selecting full flap for the landing. 

Go-around procedure 

The Cessna 206F AFM emergency section provided the balked landing (go-around) procedure:

Power – Full throttle and 2850 RPM

Wing Flaps – Retract to 20°

Airspeed 90 MPH (78 kt)

Wing flaps – Retract slowly

Cowl flaps – Open.

Additionally, the AFM provided further detail when conducting a go-around:

In a go-around climb, the wing flap setting should be reduced to 20° immediately after full power is applied. After all obstacles are cleared and once a safe altitude and airspeed are obtained, the wing flaps should only then be retracted further.

On initiating the go-around the pilot inadvertently reduced flap to the 10° setting resulting in a reduction of lift produced by the wing.

Ditching and forced landing procedure

The Cessna 206 ditching and forced landing procedure described in the AFM instructed pilots to configure the aircraft to the full-flap position so as to impact with water or terrain at the slowest possible speed. This procedure did not mention the retraction of the flaps on completion of the ditching or forced landing

Operator’s passenger safety briefing 

The operator’s exposition stated that pilots shall brief passengers about the following matters and confirm they have an understanding:

• the pilot in command is responsible for passenger safety

• safety instructions and directions from the pilot in command must be followed

• smoking tobacco, electronic cigarettes or any other substance on the aircraft is prohibited

• when seatbelts are to be worn, and how to use them

• seat backs are to be upright during take-off and landing

• how and when to adopt the brace position

• how to approach and move away from the aircraft

• entry and egress from the aircraft, including in emergency situations

• where and how to stow baggage and personal effects

• use of survival equipment / ELT as appropriate

• use of life jackets and life rafts (if carried for the operation) and that life jackets must not be inflated inside the aircraft

• restriction on the use of PEDs (personal electronic devices) and when they can be used

• communications and headset use

• if the passenger is in a flight crew seat, the requirement to ensure controls are not manipulated or interfered with

• the location of the Safety Briefing Card located at each seat.

The pilot recalled that they conducted a group briefing of the passengers prior to the first planned local area flight, with the intention of providing the passengers for the second flight an additional briefing before they boarded. 

The pilot reported they briefed the passengers on the aircraft’s seatbelts, location of the fire extinguisher, life jackets, first-aid kit and provided instruction to the front seat passenger regarding remaining clear of the flight controls. They also explained the use of both the forward left cabin door and the double cargo emergency exit doors, highlighting the red handle to open the rear cargo door. The pilot did not indicate that the passengers were briefed on actions in the event of the emergency exit being obstructed.

The adult passenger seated in the rear seat recalled seeing the handle for the forward cargo door, however they were unsure if the rear cargo door had a handle. As discussed (see Cessna 206 rear passenger emergency egress), the emergency handle is not readily visible from the rear seats in older Cessna 206 aircraft when the cargo doors are closed.

Regulatory information on emergency egress

The Cessna 206 was first certified in 1963 by the United States (US) Federal Aviation Administration (FAA). FAA regulation 14 CFR 23.2315 stated that an aeroplane is designed to: 

(a)(2) Have means of egress (openings, exits, or emergency exits), that can be readily located and opened from the inside and outside. The means of opening must be simple and obvious and marked inside and outside the airplane.

There have been a number of revisions made to this FAA design standard over the years. However, once an aircraft has been certified, the design standard under which it was certified continues to apply.

Part 90 of Civil Aviation Safety Regulations (CASR) 1998 - Additional airworthiness requirements Subpart 90.005 sets out the airworthiness requirements for an aircraft that are in addition to the type certification basis for the aircraft.

Under regulation 90.020 of CASR 1998, the Manual of Standards (MOS) sets out the additional airworthiness standards required for CASR Part 90 including, access to emergency exits.

Part 90 of the MOS stated that the minimum opening of an emergency exit must be unobstructed at all times. 

CASR 90.135 stated that each passenger must have access to at least one exit that meets the requirements prescribed by Part 90 of the MOS.

Cessna 206 rear passenger emergency egress

Background

When configured as a 6 seat-passenger aircraft, the cargo door provided the closest emergency exit for passengers seated in the rear seats and an alternate exit if the pilot’s left front cabin door became obstructed.

As discussed above in Aircraft information, when the flaps are extended, they physically block the forward cargo door from being opened beyond about 8 cm, not enabling egress.

The internal forward cargo door handle has 3 positions:

  • when the lever is horizontal (with the lever facing forward), the door is locked
  • turned clockwise 90° to the vertical position, the door is closed
  • turned clockwise another 30°, the door is opened.

With the forward door handle in the locked position the door is unable to be opened from the outside. The pilot reported that the rear seat passengers attempted to open the forward cargo door, however due to the extended flap were unable to push the door open. As the passengers were unaware of the location of the rear door handle (see Operator’s passenger safety briefing), no attempt was made to open the rear cargo door.

For the earlier models (pre-H model), including VH-TDQ, the rear door handle is a red lever (Figure 9) located in the leading edge of the rear door, which is rotated forward (to horizontal position) to open. When the forward cargo door is blocked by the flaps and the rear door handle is in the horizontal position, the rear door can only be partly opened as the horizontal handle cannot pass the forward door. The handle must then be re-stowed in the vertical position to allow the rear cargo door to pass the obstructed forward cargo door. In an emergency situation, this can and has delayed or prevented egress from the aircraft. Once the forward cargo door is slightly opened, it is possible to access the rear door handle from outside the aircraft and open the door using this process.

The pilot advised the ATSB they were aware that the forward cargo door became blocked with the flaps in an extended position. They also advised that they were aware of the requirement to open the forward cargo door before the rear door could be opened and understood the operation of both the cargo door handles. However, the pilot believed that when the flaps remained extended and blocked the forward cargo door, that the rear cargo door was unable to be opened. 

The operator’s chief pilot also reported that if the forward cargo door was blocked by the flap that passengers would be forced to egress the aircraft via the pilot’s forward left cabin door, which would be difficult for passengers seated in the rear seats.

Figure 9: Cessna U206G Cargo door

Internal image of a Cessna U206 G facing the closed cargo doors, the seats have been removed from this aircraft. Labels indicate the forward cargo door handle and obscured rear cargo door handle.

Source: TSB investigation report A18W0129, annotated by the ATSB

Cessna 206F aircraft flight manual

The emergency section of the aircraft’s flight manual contained instructions for the operation of the cargo door emergency exit which stated:

If it is necessary to use the cargo door as an emergency exit and the wing flaps are not extended, open the forward door and exit. If the wing flaps are extended, open the door in accordance with the instructions on the placard [see Figure 10] which is located on the forward cargo door.

Cessna cargo door latch service bulletin

In 1991, to assist in operating the rear cargo door from inside the aeroplane during night operations, Cessna issued Service Bulletin SEB 91-4 Cargo door latch improvement. The service bulletin recommended the installation of a return spring in the rear cargo door handle, automatically returning the handle to the closed position after opening. This assisted the rear cargo door to move freely past the blocked forward cargo door.

The service bulletin was not mandatory and was not installed on VH-TDQ.

Placard alternative

Prior to the service bulletin, due to demonstrated difficulties opening the cargo doors when the aircraft flaps remained extended during emergency situations in both Australia and overseas, the Civil Aviation Authority (CAA)[8] issued Airworthiness Directive 206/47 in 1988 that required the improvement of existing emergency exit placards for Cessna 206 aircraft in Australia (Figure 10). The placard drew attention via bold letters to step 3, to ensure the rear door handle was returned to the original position (vertical) before attempting to open the rear door (step 4). 

In 1991, when Cessna issued Service Bulletin SEB 91-4, the CAA issued Airworthiness Directive Cessna 206/47 amendment 2, which allowed SEB 91-4 to be an alternate means of compliance to the CAA emergency exit placarding. 

In 2011, CASA subsequently issued Airworthiness Directive Cessna 206/47 amendment 3, which clarified which Cessna 206 models the airworthiness directive applied to. This was due to SEB 91‑4 being incorporated by the manufacturer in some newer models, and because other models did not have the cargo door. SEB 91-4 remained as an alternate means of compliance. 

The placard was installed on VH-TDQ.

Figure 10: Forward cargo door placard 

Revised forward cargo door placard as per CASA Airworthiness Directive AD 206/47

Source: CASA Airworthiness Directive 206/47 Amendment 3

Canadian type certificate and airworthiness directive

In 1998, Cessna resumed manufacturing the 206 model aircraft with the 206H. The H model featured larger and more visible cargo door handles and incorporated SEB 91-4 for the return spring in the rear cargo door handle into the design. The forward cargo door remained blocked with flaps extended on this variant.

The 206H was certified under the US Federal Aviation Regulations 23.807. Transport Canada (TC) disagreed with the certification, stating that:

The design of the doors did not satisfy the (FAA) certification requirements that the method of opening the doors be simple and obvious and the door be readily opened, even in darkness.

As a result, in 2000 TC issued a type certificate reducing the Cessna 206H occupancy to 5 passengers.

In 2019, the Transport Safety Board of Canada issued safety advisory A18W0129-D1-A1 that stated that between 1999 and 2003, TC, the FAA and Cessna, had worked together in an effort to come up with a design change that could be applied to the Cessna 206H, which could also be used to retrofit older models of the Cessna 206 fleet. However, the matter remained unresolved and no acceptable solution was found.

In 2020 TC issued Airworthiness Directive CF-2020-10, applicable to Cessna 206 models that featured the double cargo door, stating that:

Earlier versions of the model 206 registered in Canada that feature the cargo doors have not been subject to occupancy limits, other limitations or corrective action requirements related to the cargo doors. These earlier versions of the model 206 have continued to operate in Canada without corrective or mitigating action despite the fact that the method of opening the cargo doors is essentially the same as the method for the 206H and T206H models. There is objective evidence that difficulty opening the cargo doors has contributed to fatalities during accidents in Canada involving the model 206.

The AD CF-2020-10 limited earlier model Cessna 206 to 5 occupants and required the removal of one of the middle row seats if either rear seat was to be occupied. The removal of a middle row seat provided access for passengers seated in the rear seats to the pilot’s forward left cabin door (Figure 11) for evacuation in the event the rear cargo door could not be opened quickly enough for egress. The AD also clearly stated that the vacant space left by the removal of a middle row seat must not be used for storage of cargo or baggage. 

Figure 11: Seating configuration for Canadian Cessna 206  

Diagram of the seating configuration of the Cessna 206 with a middle row seat removed improving access to the forward cabin door for occupants of the rear seats.

Source: TSB investigation report A18W0129, adapted to indicate seat removal, annotated by the ATSB

The AD also provided an alternative means of compliance through a supplemental type certificate (STC),[9] STC SA1470GL, for the installation of an additional door, on the forward right side of the cabin and was applicable to all models of the Cessna 206. This commercially available alternative means of compliance allowed Canadian registered aircraft to remain in the original 6‑seat configuration. If installed, the additional door provided immediate egress option for the passenger in the front right seat and an additional emergency egress for passengers seated in the middle row.

Australian acceptance of type certificate and supplemental type certificates

Since 1990 CASA has provided for the automatic acceptance of foreign aircraft type certificates and STC’s issued by a national aviation authority of recognised countries[10] including European Union Aviation Safety Agency (EASA).

CASA has accepted the type certificate of the national aviation authority issuing state (United States), for the following models of the Cessna 206: 206, P206, P206A, P206B, P206C, P206E, U206, U206A, 206H, U206B, U206C, U206D, U206E, U206F, U206G, T206H, TU206A, TU206C and TU206G (P206 models are not manufactured with the double cargo door).

ATSB safety recommendation

In 2020, after ATSB investigation (AO-2020-010), into an accident involving a Cessna U206G on Fraser Island, Queensland, the ATSB issued CASA with safety recommendation AO-2020-010-SR-018 recommending that CASA take safety action to address the certification basis for the design of the cabin doors in the Cessna 206, as wing extension beyond 10° will block the forward portion of the rear double cargo door, significantly hampering emergency egress.

In response CASA issued Airworthiness Bulletin 52‑006 in 2021, with a subsequent reissue in 2025. The bulletin advised pilots and operators of the impeded access from the cargo door emergency exit with the flaps extended and made recommendations that:

• Pilots should be aware that lowering the flaps may obstruct this exit and significantly increase the difficulty of opening the forward door section of the rear cargo door. All passenger pre-flight briefings should include a practical demonstration of how to open and egress the aircraft through a flap obstructed cargo door. This will require a demonstration with flaps lowered to at least 20 degrees to demonstrate the condition. Care should be taken to not damage the flap or door during this demonstration.

• Additionally, in the event that an emergency landing or water ditching is required, pilots should consider retracting the flaps if possible after the emergency landing or if operationally feasible, limit the amount of flap extension to a maximum of 10 degrees. This would of course be a judgement made by the pilot in command based on operational factors, severity of the emergency/damage to aircraft and if there are occupants seated in the rear of the aircraft.

• It is strongly recommended that registered operators and operators of affected Cessna 206, T206, TU206 and U206 aircraft series, review TC AD CF-2020-10 and give due consideration to compliance with the intent of this document, however compliance is not mandatory under CASR Part 39, because the AD is not from the state of design.

The ATSB investigation also issued Cessna a safety recommendation AO-2020-010-SR-017. The safety recommendation was to address the concern that although the Cessna 206 AFM ditching procedure required pilots to extend the flaps to the full-flap position, which resulted in a slower landing speed, this significantly impeded the emergency egress via the cargo door emergency exit and there was no warning in the AFM of the additional risk. In response, Cessna provided a temporary revision to only the Cessna 206H model AFM, providing a warning stating:

FLAP POSITIONS OF 10 DEGREES OR GREATER MAY IMPEDE EVACUATION FROM THE CARGO DOOR. FAILURE TO ADHERE TO ALL SAFETY INSTRUCTIONS CAN RESULT IN BODILY INJURY OR DEATH. 

Cessna advised the warning would be incorporated into the next revision of the Cessna 206H AFM and a placard, with the same warning would be produced for older Cessna 206 models that featured the double cargo doors. In November 2024, mandatory service bulletin SEB-11-05 was released for all Cessna 206, and U206 models prior to the 206H, for the installation of the placard on the cockpit instrument panel or another location directly visible to the pilot. The service bulletin had not been released at the time of the occurrence. 

Cessna 206 modifications to allow cargo door to open with flaps extended

Since the release of AD CF-2020-10, in 2020 TC also approved STC SA20-34 which allows the forward cargo door corner to be hinged (Figure 12). This allows the door to fold on a hinge and fully open with flap extended in any position and therefore creating no restriction to the rear cargo door.

Figure 12: Cessna split cargo door

Cessna 206 showing the approved modified forward cargo door with a hinged top part of the door allowing it to fold under the extended wing flap.

Source: Coast Dog Aviation, annotated by the ATSB

Additionally, on 2 May 2023, TC approved STC SA23-21 to provide an additional handle that is installed internally on the forward cargo door. The handle is accessible to the rear seat passengers, which, when activated jettisons the front cargo door from the aircraft. The removal of the door provided egress to the middle row occupants when flaps remained extended. The release of the door from the aircraft also improved visibility of the rear cargo door handle and simplified opening the rear cargo door for occupants seated in the rear seats.

Both STC SA20-34 and STC SA23-21 are approved as alternative means of compliance to TC CF-2020-10 and allowed Canadian registered aircraft to retain the 6 seat configuration.

VH-TDQ was not modified with the approved STC’s for the cargo door and a second forward right side door was not fitted (STC SA1470GL) and the aircraft remained in the original 6 seat configuration.

Related occurrences 

ATSB conducted a search of aviation investigation databases and other sources to identify accidents involving Cessna 206 aircraft (Appendix 1 – Cessna 206 occurrences). This search specifically looked at accidents where the impact was considered likely survivable, however where difficulties opening the cargo door resulted in significant delays during the emergency egress, or the cargo door had not been opened. 

The ATSB identified 10 occurrences that included 23 fatalities between 1985 and 2020 globally. Highlighted during the search were multiple occurrences of Cessna 206 accidents that involved fatalities when Cessna 206 aircraft were equipped with floats and operated on water. 

In March 1999, near Pitt Island, New Zealand, a Cessna 206 had an engine failure and ditched in the sea. The pilot was aware of the issue with the extended flap blocking the cargo doors and ditched the aircraft with the flaps retracted. Consequently, all the occupants escaped from the aircraft and swam to shore (New Zealand Transport Accident Investigation Commission, investigation report 99‑001) .

In January 2020, during a landing at a beach landing area on Fraser Island, Queensland, the Cessna U206G aircraft veered significantly to the left. Once airborne it was identified that the rudder was jammed in the full‑left position and the pilot had to apply full opposite aileron to maintain control. Shortly after, possibly due to fuel starvation the aircraft collided with water. Unable to open the pilot’s door the trainee pilot kicked the cargo door to force it open past the extended flap (ATSB investigation AO-2020-010).

Safety analysis

Introduction

On the morning of 1 September 2024, the pilot of a Cessna U206F, registered VH-TDQ, departed a private aircraft landing area (ALA), 21 NM (39 km) southeast of Moora, Western Australia (WA) with 5 passengers on board for a 15-minute local area flight. On return to the ALA the pilot conducted a full flap landing on the easterly runway and bounced twice. The pilot then commenced a go-around, however as the aircraft began the initial climb, the pilot inadvertently reduced the flap setting 10°. The aircraft lost height and the right wing dropped, making contact with terrain, removing the right wing tip and damaging the right aileron. The aircraft then lost speed and landed upright in a field adjacent to the runway. 

Unstable approach

As the pilot approached the ALA and was about 2 NM (3.7 km) north, they assessed that the aircraft was too high and elected to conduct a left orbit with the intention of reducing the aircraft’s height. However, no reduction in height was recorded during the orbit. 

The pilot conducted a non-standard approach to the easterly runway by joining the circuit on a base leg. This resulted in a reduction of available time for the pilot to assess the vertical descent profile effectively and likely contributed to the pilot mis-managing the short field landing with additional speed and height on the final approach.

Contributing factor

The pilot conducted a non-standard base leg join to the circuit for landing. This reduced the time available for the pilot to configure the aircraft, reduce the airspeed and prepare for a short field landing.

A combination of additional speed on final approach, the effects of a tailwind and the aircraft in the full-flap landing configuration, likely extended the aircraft’s flare. This resulted in the aircraft landing past the intended touchdown point. This also contributed to the aircraft bouncing on landing and further reduced the runway available to safely stop and likely resulted in the pilot‘s decision to go-around.

Contributing factor

Due to excessive speed on approach for a full flap, short field landing, the aircraft landed long and bounced twice.

Go-around

After the aircraft bounced a second time, the pilot commenced a go-around and applied full power to climb away. As the aircraft increased speed and began the climb out, the pilot intended to reduce the flap setting to 20° to reduce drag, but inadvertently reduced the flap setting to 10°. This resulted in a flap configuration below the prescribed setting for the aircraft’s balked landing (go‑around) procedure. 

The aircraft had not achieved the required airspeed for the lower than intended flap setting and this developed into a lack of sufficient lift and a loss of climb performance. This resulted in the aircraft losing height and directional control which caused right wingtip contact with the ground. 

Contributing factor

The pilot mis-selected the flap setting during the attempted go-around. As a result, the aircraft could not achieve adequate climb performance.

Passenger evacuation

After the aircraft came to a stop, the pilot instructed the passengers to evacuate. The front seat passenger and middle row passengers were able to egress through the pilot’s forward left cabin door. However, due to the flaps remaining extended in the 10° position, the forward half of the right-side cargo door (emergency exit) could not be fully opened. While the rear cargo door could have been opened (either from the inside or the outside), the blocking of the forward door increased the difficulty of opening the rear cargo door and caused confusion about how to evacuate the rear seat passengers.

From the inside, the rear door handle was not easily visible to passengers in the rear seats due to its obscured position and location relative to the middle row seats and the forward cargo door only able to be partially opened. Although the pilot reported providing a safety briefing to the passengers, and an aircraft placard provided instructions for the operation of the cargo door emergency exit when the flaps remained in an extended position, the adult rear seat passenger was not fully aware of the location of the rear cargo door handle.

Due to the forward cargo door being blocked by the extended wing flaps, and a rear door handle that was not easily accessible to the pilot outside the aircraft and not easily visible to passengers in the rear seats, the 2 rear seat passengers could not enact the opening of the rear emergency exit, and ultimately were required to climb over the middle row seats and egressed via the pilot’s forward left cabin door.

While this delayed a timely evacuation, in this case the rear passengers were an older adult and a young child but both capable of climbing over seats, and the pilot was able to assist from outside the aircraft. However, in emergency situations where the passengers may be less able-bodied or the pilot is incapacitated or unable to assist, the functioning of aircraft emergency exit systems must be quickly apparent and passengers must have enough awareness of their operation to ensure timely and unassisted evacuation.

Other factor that increased risk

With the flaps extended in the 10° position when the aircraft came to rest blocking the full opening of the forward cargo door, the rear seat passengers were unable to open the rear cargo door to enable an emergency exit.

In this case, there was an additional chance to evacuate via the rear emergency exit as the pilot could walk around to the outside of that exit.

As pilots of small passenger aircraft are responsible for the emergency egress of passengers, it is essential that the pilot has a full understanding of the operation of the emergency exits. Instructions for the operation of cargo door emergency exit when the flaps remained in an extended position were available on an aircraft placard.

The pilot understood that the operation of the rear cargo door was reliant on the forward door being open, and was also aware that extended flaps may block the forward cargo door. However, the pilot was unaware the rear cargo door could be opened after the forward cargo door had been made ajar (blocked by flaps). As a result, the pilot first tried (unsuccessfully) to retract the flaps, even though this was not required to open the rear cargo door. When that failed, likely due to the door remaining ajar preventing the micro‑switch activation of power to the flap system as designed, the pilot instructed the occupants to egress via the forward cargo doors over the middle row seats.

In this case, as the aircraft was not on fire nor floating on water, this lack of knowledge did not result in a worse consequence. However, in other circumstances, the inability to egress rear seat passengers from the rear emergency exit could have serious consequences.

Other factor that increased risk

The pilot was unaware that the rear cargo door on the Cessna 206 could be opened from the outside when the front cargo door was blocked by the extended flaps.

Previous ATSB and international investigations have highlighted the difficulty occupants of the Cessna 206 face egressing via the cargo door emergency exit when the aircraft flaps remain extended. While it is possible to open the rear cargo door from outside the aircraft when the forward door is blocked by the extended flaps, without training or demonstration the process is not simple or obvious. The pilot had limited experience on the aircraft type and was unaware of the process. 

Although CASA Airworthiness Bulletin 52-006 advised operators to brief passengers on emergency egress with flaps blocking the forward cargo emergency exit, the chief pilot also was unaware it was possible to open the rear cargo door when the forward cargo door was blocked by the flaps. This meant that they were unable to educate company pilots on the additional complexity operating the rear cargo door with flaps extended.

Although the company operations manual stated that pilots were required to brief passengers entry and egress from the aircraft, including in emergency situations, the operator did not provide further documentation to pilots that the passenger briefing should also demonstrate the cargo door operation with the flaps extended as recommended by CASA Airworthiness Bulletin 52-006.

The knowledge involved to demonstrate this would have provided the pilot with the correct understanding of the operation of those doors as was needed in this case. Further, had such a demonstration been conducted, it is likely that passengers seated in the rear of the aircraft would have also been aware of the location of the rear cargo door handle and process when the flaps remained extended. 

Passenger briefings therefore lacked in this regard, and in an emergency event where passengers were required to open the rear cargo/emergency doors quickly with the flaps extended, this increased the risk that the rear seat passengers would not be able to egress at all or quickly enough to escape injury.

Other factor that increased risk

The operator’s pre-flight passenger briefing did not include the demonstration of, and pilots were not trained how to operate, the emergency exit via the cargo door with the flaps extended.  (Safety Issue)

Safety advisory notice

The Australian Transport Safety Bureau advises Cessna 206 pilots and operators that due to the difficulties occupants have encountered egressing the rear cargo door as identified in several transport safety investigations, to ensure they are familiar with CASA‑issued Airworthiness Bulletin 52‑006, and ensure passengers are provided with a thorough safety briefing demonstrating the cargo door emergency egress when the wing flaps remain in the extended position.

Cessna 206 emergency egress

The Cessna 206 cargo door emergency exit has featured in numerous transport safety investigations across the world. To date, Transport Canada remains the only regulatory body that has made significant changes that improve the ease of use during an emergency. 

Transport Canada’s decision to issue an amended type certificate for the Cessna 206H when production was restarted, limited the aircraft to 5 occupants, with the required removal of a middle row seat if either rear seat was to be occupied. The subsequent release of the airworthiness directive CF-2020-10 mandated the same limitations and meant that occupants of older model Cessna 206 aircraft, particularly those seated in the rear seats, had improved access to the pilot’s forward left cabin door emergency exit. The removal of the middle row seat also improved the visibility and access to both cargo door handles for middle and rear seat occupants. 

The Civil Aviation Safety Authority (CASA) required that the aircraft emergency exits remain unobstructed at all times. Passengers seated in the rear seats of the Cessna 206 with the double cargo door are obstructed by either: 

  • the middle row seats, when attempting to access the pilots forward left cabin door
  • the flap blocking the forward cargo door when the flaps remain extended.

The majority of aircraft accidents happen during take-off or approach and landing phases of flight. During normal operation, these phases of flight usually require an amount of flap extension, therefore it becomes likely that, in the event of an accident or incident, the flaps would remain extended and hinder the use of the cargo door emergency exit. 

Previous investigations into the Cessna 206 that included fatalities of pilots who had a required knowledge of the use of an emergency exit, have found that the extended flaps blocking the cargo door contributed to the occupant’s inability to exit the aircraft during emergency egress.

The successful ditching of a Cessna 206 in New Zealand in 1999 indicated the increased occupant survivability potential when both emergency exits are clear of any obstruction.

Transport Canada has approved several modifications that provided an exemption to the occupancy limitations set out by the type certificate and airworthiness directive. This allowed the aircraft to maintain its intended 6 passenger configuration. The modifications are commercially available and improve the functionality of the emergency exits and provide access to an alternative or unobstructed emergency exit with the flaps extended.  

The extended flap blocking the forward cargo door has contributed to fatalities in previous accidents. The Cessna 206 ditching and forced landing procedure both prescribe a full-flap landing. However, unless the pilot is able to retract the flaps after the ditching or landing, the flaps would remain extended blocking the forward cargo door.

Transport Canada’s required restriction of the Cessna 206 occupancy, or the approved emergency exit modifications, reduces the risk created by the extended flaps preventing the immediate and unobstructed use of the rear cargo door emergency exit. This significantly improves the occupant’s likelihood of successful egress, during an emergency.

In Australia, CASA has provided warnings regarding the obstruction of the emergency exit and strongly recommended operators to comply with the changes that Transport Canada made. However, the aircraft’s certifying state (United States) has not mandated these changes. 

The ATSB and international transport safety investigations have highlighted the increased difficulty faced by occupants attempting to egress the Cessna 206 when the flaps remain extended. Existing approved emergency exit modifications are available to reduce the risk created by the extended flap preventing the immediate and unobstructed use of the rear cargo emergency exit. 

The approved modifications for the cargo door emergency exit would likely have resulted in occupants of the rear seats successfully opening the forward cargo door and therefore improving the ease of operation of the rear cargo door handle for the occupants or pilot. Alternatively, with a middle row seat removed, rear seat occupants’ path to the forward left cabin door would have been unobstructed.

Other factor that increased risk

The aircraft did not have the modifications detailed by CASA for Cessna 206 emergency exits, increasing the likelihood of impeded egress during emergency situations. (Safety Issue)

Safety advisory notice

The Australian Transport Safety Bureau strongly encourages operators and owners review Transport Canada Airworthiness DirectiveCF-2020-10, and consider either the removal of a middle row seat to improve rear seat occupants’ access to the pilot’s forward left cabin door or the fitment of approved Cessna 206 emergency exit modifications to reduce the risk created by the extended flap preventing the immediate and unobstructed use of the rear cargo doors during an emergency exit.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain during go‑around involving Cessna U206F, VH-TDQ, 39 km south-east of Moora, Western Australia, on 1 September 2024. 

Contributing factors

  • Due to excessive speed on approach for a full flap, short field landing, with a tail wind component, the aircraft landed long and bounced twice.
  • The pilot conducted a non-standard approach to the landing area by conducting a base leg join to the easterly runway which had a gradual upslope. This reduced the time available for the pilot to configure the aircraft, reduce airspeed and prepare for a short field landing.
  • The pilot mis-selected the flap setting during the attempted go-around. However, the aircraft could not achieve adequate climb performance.

Other factors that increased risk

  • The aircraft did not have the modifications recommended by CASA for Cessna 206 emergency exits, increasing the likelihood of impeded egress during emergency situations. (Safety issue)
  • The operator’s pre-flight passenger briefing did not include the demonstration of, and pilots were not trained how to operate, the emergency exit via the cargo door with the flaps extended. (Safety issue)
  • The pilot was unaware that the rear cargo door on the Cessna 206 could be opened from the outside when the front cargo door was blocked by the extended flaps.
  • With the flaps extended in the 10° position when the aircraft came to rest blocking the full opening of the forward cargo door, the rear seat passengers were unable to open the rear cargo door to enable an emergency exit.

Safety issues and actions

Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies. 

Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the Aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.

All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation. 

Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.

The operator’s pre-flight passenger briefing

Safety issue number: AO-2024-049-SI-01

Safety issue description: The operator’s pre-flight passenger briefing did not include the demonstration of, and pilots were not trained how to operate, the emergency exit via the cargo door with the flaps extended.

Safety advisory notice to operators and pilots of Cessna 206
SAN number:AO-2024-049-SAN-001

The Australian Transport Safety Bureau advises Cessna 206 pilots and operators that due to the difficulties occupants have encountered egressing the rear cargo door as identified in several transport safety investigations, to ensure they are familiar with CASA issued Airworthiness Bulletin 52‑006, and ensure passengers are provided with a thorough safety briefing demonstrating the cargo door emergency egress when the wing flaps remain in the extended position. 

Cessna 206 emergency exit modifications

Safety issue number: AO-2024-049-SI-02

Safety issue description: The aircraft did not have the modifications recommended by CASA for Cessna 206 emergency exits, increasing the likelihood of impeded egress during emergency situations

Safety advisory notice to operators and pilots of Cessna 206
SAN number:AO-2024-049-SAN-002

The Australian Transport Safety Bureau strongly encourages operators and owners review Transport Canada Airworthiness Directive CF-2020-10, and consider either the removal of a middle row seat to improve rear seat occupants access to the pilots forward left cabin door or the fitment of approved Cessna 206 emergency exit modifications to reduce the risk created by the extended flap preventing the immediate and unobstructed use of the rear cargo doors during an emergency exit.

Safety action not associated with an identified safety issue

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Safety action by Fly Esperance Pty Ltd

Following the occurrence Fly Esperance has made the following amendments to its operations manual: 

  • Added CASA pictorial publication ‘non-controlled aerodrome circuit procedures’ to its Circuit and landing procedures and uncontrolled aerodromes section to better clarify the process.
  • Added a table to show the recommended aircraft speed and landing weight with the flaps retracted and extended.
  • Pilots will now carry portable GPS aircraft tracking devices to improve aircraft tracking when outside ADSB coverage.
  • Greater emphasis on training including ICUS training, highlighting what can happen when standard procedures are not followed.   

The changes to the company operations manual are part of a larger amendment that will be under review by CASA in due course.

Glossary

ADAirworthiness Directive
AFMAircraft flight manual
ALAAircraft landing area
AMSLAbove mean seal level
ATSBAustralian Transport Safety Bureau
AWBAirworthiness Bulletin
CAACivil Aviation Authority (Australia)
CASACivil Aviation Safety Authority
CASRCivil Aviation Safety Regulations
FAAFederal Aviation Association
ftFeet
ktKnots
MOSManual of Standards
NAIPSNational Aeronautical Information Processing System
NMNautical miles
SEBService Bulletin
STCSupplemental type certificate
VREFLanding reference speed

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilot of the accident flight
  • Fly WA Group
  • the chief pilot of Fly WA Group
  • Civil Aviation Safety Authority
  • passengers of the accident flight
  • Textron Aviation
  • Bureau of Meterology
  • Flight Radar 24
  • accident witnesses
  • video footage of the accident flight and other photographs and videos taken on the day of the accident
  • United States Federal Aviation Administration
  • Transport Canada
  • Transport Safety Board of Canada

References

Australian Transport Safety Bureau. (2021). Collision with water involving Textron Aviation Inc. (Cessna) 206, VH-AEE, near Happy Valley, Fraser Island, Queensland, on 29 January 2020. Retrieved from /publications/investigation_reports/2020/aair/ao-2020-010#safetysummary0

Canada, T. (2020, April). Airworthiness Driective CF-2020-10. Retrieved from https://wwwapps.tc.gc.ca/Saf-Sec-Sur/2/cawis-swimn/AD_dl.aspx?ad=CF-202…

Canada, T. (2024, June). https://www.bst-tsb.gc.ca/eng/enquetes-investigations/aviation/2024/a24…. Retrieved from https://www.bst-tsb.gc.ca/eng/enquetes-investigations/aviation/2024/a24…

Civil Aviation Safety Authority. (2009). Advisory Circular AC21-30(2). Retrieved from https://www.casa.gov.au/sites/default/files/2021-08/advisory-circular-2…

Civil Aviation Safety Authority. (2017). Manual of Standards. Retrieved from Part 90: https://www.legislation.gov.au/F2010L03095/latest/text

Civil Aviation Safety Authority. (2024). Civil Aviation Safety Regulations. Retrieved from Part 90: https://www.legislation.gov.au/F1998B00220/latest/text/2

Civil Aviation Safety Authority. (2025, January). Advisory Circular AC 91-10 v1.3. Retrieved from Operations in the vicnity of non-controlled aerdromes: https://www.casa.gov.au/operations-vicinity-non-controlled-aerodromes

Civil Aviation Safety Authority. (2025). Airworthiness Bulletin 52-006. Retrieved from https://www.casa.gov.au/sites/default/files/2025-01/awb_52-006_issue_2_…

Civil Aviation Safey Authority. (2011). AIRWORTHINESS DIRECTIVE AD 206/47 amndt 3. Retrieved from https://services.casa.gov.au/airworth/airwd/ADfiles/under/cessna206/CES…

Federal Aviation Administration. (1990). Supplemental Type Ceretificates. Retrieved from SA1470GL: https://drs.faa.gov/browse/STC/doctypeDetails?modalOpened=true

Federal Aviation Administration. (2024). Delegated Organisations. Retrieved from https://www.faa.gov/other_visit/aviation_industry/designees_delegations…

Federal Aviation Administration. (2024, July 29). Federal Aviation Administration Current Regulations. Retrieved from Federal Aviation Administration: https://www.faa.gov/other_visit/aviation_industry/designees_delegations…

Transport Accident Investigation Commission, N. Z. (1999). Accident Investigation 99-001. Retrieved from https://www.taic.org.nz/sites/default/files/inquiry/documents/99-001.pdf

Wikipedia. (n.d.). Cessna. Retrieved from Wikipedia: https://en.wikipedia.org/wiki/Cessna

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the pilot of the accident flight
  • Fly Esperance chief pilot
  • Textron Aviation
  • Civil Aviation Safety Authority.

Submissions were received from:

  • the pilot of the accident flight
  • Fly Esperance chief pilot
  • Civil Aviation Safety Authority.

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Appendices

Appendix 1 – Cessna 206 occurrences

YearInjuriesSummaryLinkCountry of Occurrence
2020

2 Persons on board

(pob)

2 minor injuries

During a landing at a beach landing area on Fraser Island, Queensland, the Cessna U206G aircraft veered significantly to the left. Once airborne it was identified that the rudder was jammed in the full‑left position and the pilot had to apply full opposite aileron to maintain control. The engine subsequently stopped, possibly due to fuel starvation and the aircraft collided with water. Unable to open the pilots door the trainee pilot kicked the cargo door to force it open past the extended flap.AO-2020-010


ATSB

AO-2020-010

Australia
2018

5 pob

3 fatalities

During a landing on water, a float equipped U206G nosed over. The pilot and one passenger survived. The three remaining passengers, who received no injuries during the accident, were unable to escape the fuselage and drowned. The passengers were found with their seatbelts unfastened but had not opened the cargo door, which was blocked by 20˚ flap.

TSB

A180129

Canada
2012

5 pob

1 fatality


During a landing on water, the float equipped 206 nosed over. The flaps were extended blocking the cargo door. The pilot and three passengers escaped by bending the cargo door. The fourth passenger, found in her seat with the seatbelt on, likely died through injuries caused by the accident.

NTSB

ANC12FA073


United States
2010

5 pob

4 fatalities


During cruise, the engine failed, and the pilot conducted a ditching into Lake Michigan. The pilot did not lower the flap; however, the cargo door had not been opened. The pilot survived. Two passengers were found outside the aircraft however, their life jackets had failed. Of the two passengers found inside the cabin, one had removed their seatbelt.

NTSB 

CEN10FA465

United States
2003

2 pob

1 fatality


During the landing on water, the float equipped 206 flipped over. Contrary to instructions provided by the pilot, the passenger made their way to the rear of the aircraft, was unable to exit, and drowned.TSB aviation occurrence A03Q0083Canada
2001

5 pob

1 fatality


During the landing, the aircraft collided with a hole in the runway, nosed over and slid into a river. The pilot and three passengers escaped with minor injuries, however, one of the passengers drowned trying to escape the aircraft.Aviation Safety Network Wikibase Occurrence 45813Venezuela
19996 pobDuring an aerial surveillance air transport flight around Pitt Island, New Zealand the aircraft had a sudden engine failure and ditched in the sea. The pilot and four passengers escaped from the aircraft and swam to shore without the aid of life-jackets. Aircraft flaps were not extended during the ditching.Transport Accident Investigation Commission, New Zealand 99-001New Zealand
1997

3 pob

2 fatalities


During the landing on water, the float‑equipped aircraft flipped as the landing gear had not been retracted. Two passengers were unable to exit the aircraft and drowned. The door handle was found in the upright closed position.TSB Aviation investigation report A97C0090Canada
1996

6 pob

4 fatalities


During the take-off on water, the aircraft capsized. The pilot and three passengers drowned in the rear of the aircraft, when the pilot could not open the cargo door. Two passengers escaped through the pilot door. There was evidence that an adult had attempted to open the cargo door.TSB Aviation investigation report A96Q0114Canada
1989

5 pob

4 fatalities


During the landing on a dam, the float‑equipped 206 nosed over as the landing gear had not been retracted. The pilot and one passenger survived, but three passengers were fatally injured.Aircraft Accident Investigation Board – Norway 06/99Norway
1985

5 pob

3 fatalities


During the landing on a dam, the float‑equipped 206 nosed over as the landing gear had not been retracted. The pilot and one passenger survived, but three passengers were fatally injured.

ATSB 

198503550

Australia

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

CC BY logo

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Flap: lift devices mounted on the wing trailing edge.

[2]     Go-around: a flight path taken by an aircraft after an aborted approach to landing.

[3]     Battery master: provides electrical power from the battery to the aircraft systems.

[4]     NAIPS: National Aeronautical Information Processing System

[5]     Runway direction indicating a magnetic heading.

[6]     Flight Radar 24 height data is accurate to within 100 ft.

[7]     VREF: landing reference speed.

[8]     The CAA became CASA in 1995.

[9]     A supplementary type certificate (STC) is a form of regulatory approval of the design of a major modification, or collection of changes, to a type certificated aircraft, aircraft engine or propeller.

[10]    Recognised countries include Canada, Federal Republic of Germany, New Zealand, The French Republic, Kingdom of the Netherlands, The United Kingdom and The United States of America.

Occurrence summary

Investigation number AO-2024-049
Occurrence date 01/09/2024
Location 39 km south-east of Moora
State Western Australia
Report release date 30/06/2025
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Control issues, Incorrect configuration, Missed approach
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Cessna Aircraft Company
Model U206F
Registration VH-TDQ
Serial number U20602807
Aircraft operator Fly Esperance Pty Ltd
Sector Piston
Operation type Part 135 Air transport operations - smaller aeroplanes
Departure point Private ALA, north-east of New Norcia
Destination Private ALA, north-east of New Norcia
Damage Minor

Collision with terrain involving Extra EA 300-LT, VH-XKW, about 10 km west-south-west of Bathurst Airport, New South Wales, on 13 October 2024

Final report

Report release date: 10/04/2025

Investigation summary

What happened

On 13 October 2024, an Extra EA 300-LT aircraft, registered VH‑XKW, with a single pilot on board, departed from Bathurst Airport to conduct a trophy delivery at the annual Bathurst 1000 motor race, at the Mount Panorama circuit, about 10 km west‑south‑west of the airport. After landing on Mountain Straight (the location of the trophy handover), the aircraft collided with a concrete barrier. Following the trophy handover, the aircraft departed overhead spectator stands with a damaged tailplane.

What the ATSB found

The ATSB found that in preparing for the event, the pilot planned to land and take-off over a designated NO FLY AREA occupied by spectators, which did not comply with the Civil Aviation Safety Authority’s (CASA) required spectator safety heights and distances for an air display. The aircraft struck a barrier after landing on Mountain Straight during a reversal turn resulting in damage to the tailplane. However, following advice of the impact from a media helicopter, the pilot did not conduct an external inspection and subsequently departed overhead a spectator NO FLY AREA.

The ATSB also found that the CASA inspector approved the pilot’s application to land and take‑off from Mountain Straight, despite limited information from the applicant and the published safety constraints of the NO FLY AREAs surrounding the planned landing area.

Safety message

The CASA‑published Advisory Circular 91-21 describes the safety requirements for air displays and provides the guidance for completing air display applications. As expressed in AC 91-21, while the level of risk for air display participants may be elevated, the displays must be planned and conducted such that they do not increase the level of risk for spectators and other uninvolved parties.

All air display personnel, such as the organiser, air/ground coordinator(s) and participant(s), should ensure that air displays are not only planned to be in compliance with those requirements, but that they are also conducted in a way that is consistent with the approved arrangements. 


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

At 0953 local time on 13 October 2024, an Extra EA 300-LT aircraft, registered VH-XKW, with a single pilot on board, departed from Bathurst Airport to conduct a trophy delivery at the annual Bathurst 1000 car race. Recorded data indicated that after take-off, the aircraft proceeded to a holding area where it arrived at 0956. After completing a left and right orbit, the aircraft left the holding area in the company of a media helicopter filming the trophy delivery event. The aircraft then commenced a left hand circuit to line‑up for a landing in the southerly direction on the Mountain Straight section of the Mount Panorama motor racing circuit, about 10 km west‑south‑west of the airport, where the trophy was to be delivered (Figure 1).

Figure 1: Landing and take-off of incident flight between Bathurst Airport and Mount Panorama

Figure 1: Landing and take-off of incident flight between Bathurst Airport and Mount Panorama

Source: Pilot’s OzRunways data and Google Earth, annotated by the ATSB

At 1003, the aircraft lined up on a 1 NM final approach at an altitude of about 2,900 ft. At this time, Bathurst Airport recorded a wind velocity of 7 kt from 071° True (T) after a peak of 13 kt from 048° T at 0959. The pilot reported there was a crosswind from the left and a small tailwind component on final, but that they were within the aircraft limits and there were no wind gusts. The aircraft arrived overhead the start of Mountain Straight at an altitude of about 2,402 ft (50 ft above ground level) with a groundspeed of 89 kt, after passing overhead spectators on short final, before landing on the grass to the left of the bitumen. The pilot then manoeuvred the aircraft to the right from the grass onto the bitumen as it continued to slow while travelling uphill along the straight.

The racetrack barriers on either side of Mountain Straight narrowed in the southerly direction and the pilot reported that in the narrower section the aircraft would need the additional space of a driveway entrance to turn around.[1] After manoeuvring the aircraft onto the bitumen, the pilot decided to turn the aircraft around before the narrow section and attempted what they described as an ‘aggressive’ turn, which was a right turn followed by a left reversal turn.

Footage and recorded data of the landing indicated that the left wheel moved off the left edge of the bitumen at a groundspeed of about 27 kt just before the aircraft veered right and traversed the bitumen track from left to right. The aircraft slowed to about 13 kt groundspeed when the right wheel exited the bitumen onto the grass on the right side of the track. The aircraft then spun around about 90° to the left before the right rear corner of the tailplane impacted the concrete track barrier and stopped the aircraft. At the time, the aircraft was about 530 m along the straight from the 50 ft threshold height. Engine power then increased, and the aircraft moved away from the barricade, completed the left reversal turn and taxied down the straight, in the opposite direction to the landing, to the location of the trophy delivery, with damage to the right rear corner of the tailplane (Figure 2).

Figure 2: Tailplane damage after collision

Figure 2: Tailplane damage after collision

Source: YouTube, modified and annotated by the ATSB

The camera operator in the media helicopter saw the aircraft’s tail impact the barrier during the turn and immediately reported this to the media helicopter pilot. The media helicopter pilot in turn immediately informed the incident pilot of the collision over the radio and recommended the pilot check the aircraft’s tail before take-off. The pilot contacted their team member at the track via radio, but reported at interview that the team member could not observe the collision. The pilot also reported that they did not feel the contact with the barrier, and that after the trophy was delivered, a full control check was conducted on the ground as well as a visual check of the tail from their cockpit seated position, with no control problems or visible damage identified.

The pilot then taxied the aircraft back uphill along Mountain Straight, turned around to line‑up in the northerly direction (opposite to the landing direction), and departed overhead the spectators to return to Bathurst Airport. After arrival at the airport, the pilot saw the damage to the tailplane and contacted the Civil Aviation Safety Authority (CASA) in response to a request for information about the incident.

Context

Pilot information

The pilot held a recreational pilot licence (aeroplane), issued by CASA in January 2019, with the required ratings and endorsements to operate the Extra EA 300‑LT and a current class 2 aviation medical certificate. The pilot’s last flight review in May 2023 included an activity endorsement to conduct aerobatics to a lower limit of 500 ft above ground level. The pilot reported that they had accumulated about 800 hours of flying experience, which included 320 hours operating the Extra. The pilot provided a fatigue self-assessment score of ‘1 – fully alert’ for the time of the accident. 

Meteorological information

The 1000 METAR[2] for Bathurst Airport, which has an elevation of 2,435 ft, provided a wind velocity of 10 kt from 050° T, visibility greater than 10 km, cloud base broken at 2,900 ft above the airport elevation, temperature of 15°C and QNH[3] of 1026 hPa. This resulted in a pressure altitude of 2,001 ft and density altitude of 2,476 ft for the start of Mountain Straight. The 1‑minute wind data recordings for the period 0945–1015 indicated the wind direction varied from 016°–077° T, and the speed varied from 7–13 kt. At the time of the aircraft’s final approach and landing between 1003 and 1004, the recorded wind velocities at Bathurst Airport were 071° at 7 kt (1003) and 050° at 7 kt (1004).

Mountain Straight

Mountain Straight is oriented 190° T / 010° T and is about 1,111 m in length from the northern end at Hell Corner, just after Pit Straight, to the first turn at Griffins Bend.[4] It climbs in a southerly direction towards Griffins Bend, with an average gradient of about 5.4% (Figure 3). The northern (lower) half of the straight is about 20 m wide between the western edge of the bitumen track and the barriers on the eastern side of the track. The width reduces to about 8–10 m for the southern (upper) half of the straight, starting about 585 m from the northern end, where there is trackside tree coverage and co-located infrastructure leading to Griffins Bend.

Figure 3: View of Mountain Straight looking to the south with VH-XKW on approach

Figure 3: View of Mountain Straight looking to the south with VH-XKW on approach

Source: YouTube, annotated by the ATSB

Aircraft information

General information

The Extra Flugzeugproduktions – und Vertriebs EA 300-LT aircraft was a tandem, 2-seat aerobatic monoplane with the rear seat instrumented for the pilot. It was built with a steel-tube construction and composite material for the wings, empennage and landing gear, designed for unlimited acrobatics up to +/-10 G and was operated under a special certificate of airworthiness in the experimental category. 

Performance information

The pilot operating handbook indicated that the aircraft’s final approach speed in the lower weight category of 820 kg (single-pilot using centre fuel tank) was 79 kt indicated airspeed. The calculated landing distance over a 50 ft obstacle at 79 kt on a concrete runway with maximum braking was 591 m at 2,000 ft pressure altitude and a temperature of 15°C, with a 193 m landing roll. The landing roll increased by 15% on dry grass due to the reduced braking efficiency, which increased the landing distance to 620 m.

The performance tables did not provide a correction factor for an upslope landing or a tailwind and therefore, the actual landing distance required on the day could not be determined. The performance tables also did not provide a correction factor for a downslope landing. However, an increase of 5% to the landing distance for each 1% of the average slope (5.4%) would result in a downslope landing distance of 751 m with maximum braking on bitumen.[5]

Practice day

The pilot was provided a practice opportunity for the air display on 10 October, which included a practice landing and take-off from Mountain Straight. The pilot conducted the practice landing onto the bitumen, which required an approach over a tree on the western side of the track, near the northern end of the straight, and a rollout along the upper narrow section of track to a driveway for the turnaround. On 12 October, the pilot re-inspected Mountain Straight on the ground and decided to modify the approach and touchdown to land on the grass on the eastern side of the bitumen to be closer to the northern end of the straight and the location of the trophy handover.

Air display applications and approvals

Applications

Prior to conducting an air display, the organiser, who can be the pilot conducting the display, must apply to CASA with supporting attachments (CASR form 91.180) for approval to conduct the display. To assist in the preparation of the supporting attachments, CASA published advisory circular AC 91-21 Air displays in November 2022 and the circular was referenced in CASR form 91.180 wherever an attachment was required. Several sections of AC 91-21 were relevant to the pilot’s application for Bathurst including:

3.4 Events that organisers are planning for the first time

3.4.4 For an air display approval, CASA's test of safety is that the display will result in the preservation of a level of aviation safety that is at least acceptable given the circumstances. CASA acknowledges that the level of risk for some air displays, for the persons onboard the aircraft, is elevated compared to more routine private operations. However, air displays are to be planned to not increase the level of risk for uninvolved parties, such as spectators, compared to routine private operations.

5.3 Display Coordinator

5.3.1 The display coordinator is appointed by, and responsible to, the display organiser. The display coordinator controls the actual flying program and assumes overall responsibility for the airborne component and safety of the display event.

5.3.2 The documentation submitted to CASA for an air display approval must include the details of the display coordinator.

5.6 Ground Control Coordinator

5.6.1 The ground control coordinator is an essential component of a fly-in, competition or air display. The ground control coordinator should have a considerable and verifiable aviation background, commensurate with the planned event, that enables them to identify aviation ground-based hazards and their impact on persons and property during the event and are responsible to the Display Organiser.

9.3 Manoeuvring limitations

9.3.1 Aircraft used in an air display are subject to the following manoeuvring limitations:

• except where specifically requested as part of the program of events and then part of the approval, an aircraft in flight below 1 500 ft AGL must not:

     ◦ track or manoeuvre towards spectators within a horizontal distance of 500 m; or

     ◦ pass within 200 m horizontal distance from spectators. 

9.7 Weather minima

9.7.1 Minimum weather conditions must be determined by the display organiser in advance of the air display, published in the display instructions and strictly observed. This makes the decision to cancel the display in the event of bad weather less subjective and minimises pressure on the display organiser to proceed with the display in less than favourable conditions.

Approvals

The CASA air display application form CASR 91.180 (with any applicable attachments) was to be submitted to CASA Regulatory Services, who allocated assessment of the application to a CASA team in the region where the air display was planned to occur. The task was then allocated to a Flight Operations Inspector (FOI) who had completed the CASA training course for air displays. The FOI was required to assess the application guided by a CASA worksheet (OPS.25) and to communicate with the applicant to seek more information if required or to challenge the application’s compliance with the requirements of AC 91-21. The FOI was required to record the answers to the worksheet’s questions as well as their assessment decision with their reasoning. If the FOI recommended approval of the air display application, CASA subsequently sent the applicant their instrument to conduct the air display.

Pilot’s air display applications

Prior to the Bathurst event, the pilot submitted 2 air display applications in 2024 for motor racing events, with a planned landing and take-off on the racetrack for events in Perth in May (Barbagallo racetrack) and Melbourne in September (Sandown racetrack).

Perth SuperSprint – May 2024

The initial application for the Perth event was submitted by a third party on behalf of the pilot and included a landing on the Barbagallo racetrack back straight on 17 May followed by a take-off from the main (front) straight on 18 May. The application’s appended risk assessment included the landing and take-off area dimensions and a crosswind limit of 12 kt for the landing and was otherwise consistent with the sample risk assessment in appendix C of AC 91-21. However, it did not address the AC 91-21 manoeuvring limitation safety distances for spectators for the proposed landing and take-off. The risk assessment included the presence of an ‘air-boss’ who could call STOP DISPLAY, a ground observer who could call STOP DISPLAY and a display coach who would provide ‘go / no-go authority’. The initial display diagram in the application did not identify the landing and take-off areas. 

When the initial application was received, CASA assigned the assessment task to an FOI who contacted the pilot via email on 5 April, to introduce themselves and provide a list of questions and items that needed rectification. The following requests for clarification from the first review were of relevance to the Bathurst incident:

  • If the pilot is the organiser and will be flying, who will be handed control of the event when the pilot is in the air?
  • For the landing and take-off, CASA needed to see the area in person to ensure conformance with reg 91.410 of CASR 1998, AMC/GM 91.410 and AC 91-02 Guidelines for aeroplanes with MTOW not exceeding 5700kg – suitable places to take-off and land.
  • The Display Lines and AXIS diagrams needed to clearly show the requirements of section 9.3 [Manoeuvring limitations] and 9.4 [Display lines] of AC 91-21 Air Displays.
  • The identities of the personnel linked to the display, including the air boss, were required on the application.

The documents were resubmitted, and after a second review, CASA sent the pilot another email on 16 April. This reiterated a number of their initial concerns plus additional items that needed to be addressed, which included prohibiting use of the front straight for take-off and confirmation that the aircraft would not be manoeuvred towards spectators in accordance with the limits in AC 91‑21.

On 8 May, the FOI sent another email to the pilot after completing a third review of the submission and suggested a telecommunications meeting to help resolve the outstanding matters. The subsequent revisions to the display diagram identified the relevant straights for the planned landing, taxi and take-off along with the spectator areas and display box. Two CASA inspectors then attended the racetrack on 10 May to inspect the suitability of the back straight for a landing and take-off. The display application was subsequently approved on 13 May. Throughout their correspondence, the FOI repeatedly requested the pilot address the spectator safety distances in AC 91-21 in their application.

The completed OPS.25 worksheet included several restrictions that had been imposed as part of the application review process, including restricting the landing and take-off to the back straight. In their reason for recommendation, the FOI noted that the assessment took longer than usual but was treated as educational as they expected an increase in display applications from the pilot in the future.

Sandown 500 Supercars Championship – September 2024

On 21 August, the pilot applied to CASA Regulatory Services for an air display approval for the Sandown event in Melbourne. The application included a display summary attachment which indicated a proposed landing and take‑off from the Sandown track main straight on 15 September for a trophy handover and noted that there would be an experienced aerobatics pilot at the track acting as the display coordinator for the event. However, the display diagram did not identify the approach and departure or spectator NO FLY AREAs. The only recorded risk in the application associated with the trophy handover was ‘Landing with people on track’ and there was no information about the suitability of the main straight for landing and take-off despite this being a source of concern for CASA during the application process for the Perth event.

On 3 September, the CASA FOI who was assigned the task sent the pilot their first round of feedback to the application. The first item listed was that CASA would not issue a display approval while it included a landing and take-off from the main straight as it did not meet the manoeuvring limitations for operations towards, and parallel to, spectators. They also highlighted the need for the display axis in the display diagram to provide adequate safety margins from spectators and populous areas.

On 4 September, the track landing was removed from the display summary and resubmitted to CASA. On 5 September, the FOI requested a copy of the pilot’s updated display diagram, to which the pilot responded with a proposed display axis that crossed the main straight and spectator stands. The FOI then sent the pilot a Google Earth image with a 500 m arc depicting the area where the pilot could not fly towards the spectator stands and a 200 m line depicting the minimum distance the display axis needed to be from the spectator stands in accordance with AC 91-21. The pilot then submitted an updated display diagram that complied with the requirements. CASA issued the pilot with the instrument to conduct the air display on 9 September.

The OPS.25 worksheet included the restriction that there was to be no landing and take-off operations at the Sandown track. Within their reason for recommending approval, the FOI reported that the plan to land on the main straight was ‘rejected as not meeting air display regulatory requirements’, that the display axis was changed to meet the ‘air display requirements in relation to spectators’ and that ‘the applicant was receptive and cooperative during the lengthy assessment process.’

Bathurst 1000 – October 2024

On 30 August, the pilot submitted an air display application for the 2024 Bathurst 1000 motor racing event. The application named the same display coordinator as for the Sandown air display event and included a landing and take-off from Mountain Straight on 13 October and aerobatic displays on 11 and 12 October. The display coordinator was also identified as the ‘ground-boss’ for the display and was:

  • responsible for clearing the pilot for the landing and take-off from the track
  • responsible for monitoring other traffic during the aerobatics displays
  • a member of the emergency response plan and had STOP DISPLAY responsibilities within the risk assessment.

Despite being assigned these responsibilities, the nominated display coordinator reported to the ATSB that, while they agreed to support the Sandown event, they were not at the Bathurst event and were unaware they had been nominated by the pilot on the Bathurst display application submitted to CASA.

The display diagram in the application included the pilot’s aerobatic display axis and the spectator NO FLY AREAs, located inside and outside of the track (Figure 4). The northern end of Mountain Straight was surrounded by NO FLY AREAs but the display diagram did not include the planned approach and departure paths over those areas. Similar to the Sandown risk assessment, the only risk associated with the trophy handover was ‘Landing with people on track’.

There was no information about the dimensions and suitability of the proposed landing area, spectator safety distances or weather limits. The pilot advised the ATSB that the race organisers had a spare trophy at the track if the landing had to be aborted and an off‑track parking location if the aircraft became unserviceable after landing. These measures were in place to mitigate the pressure to land and take-off in unfavourable circumstances but were not included in the risk assessment.

Figure 4: Pilot’s display diagram

Figure 4: Pilot’s display diagram

Source: Civil Aviation Safety Authority, annotated by the ATSB

On 5 September, CASA acknowledged receipt of the pilot’s application by email, and provided the pilot with the contact details of the FOI assigned to assess the request. The FOI reported to the ATSB that on review of the application, they assumed the pilot would comply with the NO FLY AREAs on the display diagram and that they were unaware of the topography of Mountain Straight.

The FOI did not review any of the pilot’s previous applications and therefore was not aware of the requests to conduct landings and take-offs at the Barbagallo and Sandown racetracks. On 6 September, the FOI issued the display approval without any requests for information or clarification from the pilot and without completing the required OPS.25 worksheet.

Safety analysis

The pilot submitted an air display application with a proposed landing and take-off from Mountain Straight for a trophy handover and a display diagram with NO FLY AREAs annotated surrounding the northern end of Mountain Straight. The pilot marked the display diagram with their proposed aerobatic display axis and submitted this to CASA, which indicated the pilot was aware of the NO FLY AREAs surrounding the track. However, they did not include their approach and departure flightpaths on their display diagram or display summary. The pilot subsequently reported at interview that it was their plan to land uphill and take-off downhill. This needed to be conducted at the northern end of Mountain Straight due to the obstructions alongside the southern end. However, this plan breached the spectator safety distances in AC 91-21, which CASA had brought to the pilot’s attention during interactions as part of their previous track landing applications.

After a practice flight and landing, the pilot moved the touchdown point from the bitumen to the grass, in order to shorten the backtrack for the trophy handover. However, on the day, there was a tailwind component for the landing, which resulted in the aircraft approaching the narrower upper‑half section of track before the pilot was able to reduce the groundspeed sufficiently to control their reversal turn. This contributed to the tailplane impacting the concrete barrier during the turn. While crosswind and tailwind were reportedly within the allowable aircraft limits, the pilot acknowledged the approach should not have been conducted with a tailwind component. The absence of any weather limits for the landing in the display application, or provided by the pilot at interview, indicated the decision to conduct the approach with a tailwind was likely the result of inadequate planning.

The landing and impact with the barrier were captured live by a media helicopter crew, who immediately reported the collision to the incident pilot with a recommendation to inspect the tailplane before take-off. However, the pilot elected not to shutdown the aircraft and exit for an external inspection, or request their team member conduct an inspection, and instead departed overhead the crowd with a damaged tailplane. The pilot had nominated an experienced aerobatic pilot as the display coordinator with authority to stop the display. However, this person was not at the event and was not aware they had been nominated. Therefore, they were unable to challenge the planning or exercise their authority to stop the display after the media helicopter pilot alerted the incident pilot to the collision over the radio.

Air displays are subject to CASA approval, which can include conditions on the display, and in the past CASA had modified or rejected the pilot’s applications to land on a track. This included the Perth SuperSprint event, where the pilot was prohibited from taking off from the front straight, and the Sandown Supercars event where the pilot was prohibited from conducting a track landing due to the elevated risk to those on the ground and co-located infrastructure on the main straight.

The pilot’s Bathurst display application did not include how the landing and take-off would be conducted without breaching the NO FLY AREAs. While the FOI was reportedly unaware of the topography of Mountain Straight, they assumed the pilot would comply with the NO FLY AREAs and that the nominated display coordinator would be in attendance. Consequently, the FOI did not question the pilot’s planning or check the topography, either one of which would have revealed that the spectator safety distance could not be met while landing on the proposed section of the racetrack. In addition, a check of the pilot’s previous air display applications would have revealed they had a history of difficulty applying the requirements of AC 91-21 to their display planning.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving Extra EA 300-LT, VH-XKW, about 10 km west-south-west of Bathurst Airport, New South Wales on 13 October 2024. 

Contributing factors

  • The pilot planned to land and take-off over a NO FLY AREA occupied by spectators, which breached the required air display spectator safety heights and distances.
  • The aircraft struck a barrier during a reversal turn after landing on Mountain Straight, resulting in damage to the tailplane. Following advice of the impact, the pilot did not conduct an external inspection and subsequently departed overhead a spectator NO FLY AREA.
  • The Civil Aviation Safety Authority’s inspector approved the pilot’s application to land and take‑off from Mountain Straight despite limited information from the applicant and the constraints of the NO FLY AREAs surrounding Mountain Straight.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • Bathurst Regional Council website
  • Civil Aviation Safety Authority
  • European Union Aviation Safety Agency website
  • Google Earth
  • OzRunways recorded data from incident pilot
  • the involved pilot
  • the pilot of the media helicopter
  • the nominated display coordinator
  • witness video footage and reports
  • YouTube.

References

Civil Aviation Safety Authority (2024) Air displays (Advisory Circular 91-21, v2.2), October 2024, Canberra.

European Union Aviation Safety Agency (2023) Easy access rules for air operations (IR & AMC/GM & CS/GM), retrieved from Easy Access Rules for Air Operations - Revision 21, September 2023 | EASA

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the involved pilot
  • Civil Aviation Safety Authority.

A submission was received from:

  • Civil Aviation Safety Authority.

The submission was reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]      According to the Bathurst Regional Council website, the Mount Panorama circuit is a public road subject to track closures with private residences located inside and outside the track.

[2]      METAR: a routine aerodrome weather report issued at routine times, hourly or half-hourly.

[3]      QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean seal level.

[4]      Naming convention according to the Bathurst Regional Council website.

[5]      European Union Aviation Safety Agency acceptable means of compliance (AMC2 CAT.POL.A.330 Landing – dry runways): Unless otherwise specified in the AFM, or other performance or operating manuals from the manufacturer, the landing distances required should be increased by 5% for each 1% of downslope.

Occurrence summary

Investigation number AO-2024-052
Occurrence date 13/10/2024
Location About 10 km west-south-west of Bathurst Airport
State New South Wales
Report release date 10/04/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Extra-Flugzeugbau GmbH
Model EA 300/LT
Registration VH-XKW
Serial number LT001
Aircraft operator HP Automotive Pty Ltd
Sector Piston
Operation type Part 91 General operating and flight rules
Departure point Bathurst Airport, New South Wales
Destination Bathurst Airport, New South Wales
Damage Minor

Collision with terrain involving Kawasaki KH-4, VH-BEU, 24 km north of Katherine Tindal Airport, Northern Territory, on 11 September 2024

Final report

Report release date: 09/05/2025

Investigation summary

What happened

On the afternoon of 11 September 2024, the pilot of a Kawasaki 47GB3‑KH4, registered VH‑BEU and operated by Katherine Helicopters, was conducting a scenic flight over Nitmiluk (Katherine) Gorge, Northern Territory with 2 passengers on board. 

About 13 minutes into the flight, while entering the mouth of the gorge, the pilot reported experiencing an engine power loss and lack of response from the engine. Due to inhospitable terrain in the area, the pilot identified a clear landing spot some distance away and attempted a forced landing at that location, during which time the aircraft collided with terrain.

The pilot and both passengers were uninjured in the incident, however, the aircraft was substantially damaged.

What the ATSB found

Several possibilities were considered during the investigation in relation to the reported engine power loss. While the ATSB did not conduct a physical inspection of the engine in this instance, a post‑incident inspection revealed that a large crack had developed in the engine exhaust pipework. Being a turbocharged engine, the escape of exhaust gases through the crack during operation has likely resulted in an engine power loss during flight due to the loss of boost pressure.

The ATSB also identified that the pilot was unable to cushion the landing during termination of the autorotation, likely due to low main rotor RPM, resulting in the helicopter colliding with terrain.

Safety message

Helicopter operations over harsh terrain offer limited safe emergency landing options. Autorotation to a suitable area in such circumstances requires accurate helicopter positioning and energy maintenance (airspeed and rotor RPM). This makes thorough and regular training in emergency procedures crucial for pilots operating in these demanding environments. The prompt action taken by the pilot, in identifying a suitable landing site, was instrumental in ensuring the safety of all personnel on board.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 11 September 2024, the pilot of a Kawasaki Heavy Industries 47GB3‑KH4, registered VH‑BEU and operated by Katherine Helicopters, was conducting scenic flights over Nitmiluk (Katherine) Gorge, Northern Territory.

During the morning, the pilot conducted the required daily checks on the helicopter and completed a passenger flight over the gorge (Figure 1). After returning to base, the pilot refuelled the helicopter and completed short, uneventful ferry flights to Katherine Museum and return.

Figure 1: Nitmiluk (Katherine) Gorge scenic flight overview 

Figure 1: Nitmiluk (Katherine) Gorge scenic flight overview

Source: Google Earth, annotated by the ATSB

That afternoon, the pilot met 2 passengers at the operator’s base, and then completed the flight manifest including the passengers’ weight details, based on verbal information provided by the passengers. The pilot carried out their pre-departure checks, including a flat‑pitch check,[1] which were all normal. A safety briefing was also undertaken with both passengers, which reportedly included:

  • use of seatbelts
  • in‑flight procedures
  • operation of the doors and emergency exits
  • actions to be taken in case of an emergency.

At around 1451 local time, the helicopter departed and after making a turn towards the north, the pilot gradually climbed to about 1,000 ft above mean sea level (AMSL), proceeding north‑easterly along the Katherine River in the direction of the gorge.

About 10 minutes later, the pilot climbed further to a height of about 1,400‍–‍1,500 ft AMSL to fly neighbourly[2] while approaching the escarpment bordering Nitmiluk National Park (Figure 2). The pilot then arranged separation with the pilot of a second helicopter in the area, using the common traffic advisory frequency (CTAF).

Figure 2: View from helicopter of Nitmiluk National Park

Figure 2: View from helicopter of Nitmiluk National Park

Source: Passenger photograph, annotated by the ATSB

Approximately 3 minutes later, as the helicopter was entering the mouth of the gorge, the pilot noticed that the engine did not respond when they increased the throttle, and that the helicopter was decelerating and losing height. Due to being overhead undulating rocky terrain, the pilot commenced a right turn in search of a suitable landing site, in case they had to conduct a landing (Figure 3).

The pilot reported that the ensuing events occurred extremely quickly. While turning around, the helicopter kept slowing and the engine did not respond to throttle movements. They noticed a significant change in the engine noise, described as a low‑pitched ‘whir’ sound, and reported feeling stiffness in the pedals. Not knowing what was wrong with the engine, the pilot lowered the collective[3] and entered autorotation (see the section titled Autorotation). 

During the descent, the pilot glanced at the instruments and noted that the engine RPM needle was split[4] from the main rotor RPM needle and again tried unsuccessfully to increase the throttle. The pilot later advised that the main rotor RPM was well below the green arc on the gauge, and the engine RPM was just below idle. The pilot reported identifying a landing site in a clearing about 400‍–‍500 m to the west of their location and broadcast a MAYDAY[5] call on the CTAF. 

The helicopter proceeded downwind towards the clearing, attaining a maximum groundspeed in excess of 83 kt. Given the prevailing wind, that equated to an airspeed of about 70 kt, which was higher than the recommended autorotation speed for the helicopter type (see the section titled Autorotation). However, during the final approach to the selected landing site, the groundspeed, and given the crosswind approach, also airspeed was reduced to about 50 kt.

Figure 3: Helicopter flight path with identified elevation and ground speed

Figure 3: Helicopter flight path with identified elevation and ground speed

Source: OzRunways data on Google Earth, annotated by the ATSB 

The passengers reported that during the descent, communication from the pilot was minimal. They were not advised by the pilot to brace for impact; however, upon hearing the MAYDAY call and seeing the pilot attempt an unexpected landing, both passengers suspected that an emergency situation had developed, and chose not to interrupt the pilot or distract them from their actions.

The pilot reported that, on nearing the landing site, they attempted to flare the helicopter but there was minimal flare effect, which they assessed was most likely due to low main rotor RPM. Consequently, the pilot attempted a run‑on landing, during which the helicopter collided with terrain, damaging its tail rotor/shaft and skids (Figure 4).

Figure 4: Helicopter accident site

Figure 4: Helicopter accident site

Source: Operator 

After landing, the pilot shut off the fuel, magnetos and battery. After checking on the passengers, the pilot disembarked the aircraft, ensured it was safe to exit with the main rotor blades still rotating, and then instructed the passengers to evacuate the aircraft. The pilot of the other helicopter operating in the area repeated the MAYDAY call on the area frequency and then circled overhead the accident site. A rescue crew arrived onsite shortly after and the pilot and both passengers were evacuated uninjured.

Context

Pilot information

The pilot held a commercial pilot licence (helicopter) and a class 1 aviation medical certificate. At the time of the incident, they had accumulated about 380 hours total aeronautical experience. All the pilot’s training and most of their flying experience has been obtained operating Robinson R44 helicopters. They had been flying for Katherine Helicopters for about 3 months. 

While at Katherine Helicopters, the pilot received their Bell 47 endorsement after undergoing about 3 hours of training with an instructor that included the conduct of emergency procedures. The pilot also performed about 10 hours of in command under supervision (ICUS)[6] training with the operator.

Operator information

The operator was a helicopter tour operator based in Katherine, Northern Territory. It operated 2 Bell/Kawasaki 47 Helicopters and offered tour flights throughout northern Australia. 

Previous incidents 

The pilot had been involved in another engine failure incident on a second helicopter of the same type with the operator in July 2024, wherein an engine cylinder failed. The pilot completed a successful autorotation and there were no reported injuries. While this matter was reported to the ATSB, it was not investigated.

In addition to the incident above, the other helicopter operated by the operator was involved in a third off field landing, arising from an engine fault, in February 2024. 

Helicopter information     

The helicopter was a Kawasaki Heavy Industries 47G3B‑KH4, manufactured in 1969 in Japan by Kawasaki Heavy Industries and first registered in Australia on 20 June 1996. At the time of the accident, VH‑BEU had about 7,495 hours total time in service and had flown about 40 hours since its last periodic service inspection. 

Engine and turbocharger system

VH‑BEU was powered by a Textron Lycoming TVO‑435, 6‑cylinder, vertical direct drive, horizontally opposed, turbocharged engine. The turbocharger increases the density of the carburettor inlet air to maintain the available power as altitude increases. 

During operation, the exhaust gases expelled from the 3 cylinders on either side of the engine are merged into a single pipe, through which the gases are diverted either to the turbocharger or to the exhaust bypass valve (waste gate), or both (Figure 5).

As the engine power is increased, oil pressure builds up in the exhaust bypass valve assembly and the waste gate in the exhaust system is closed. This diverts the exhaust gas to the turbocharger turbine wheel, compressing the intake air and increasing the available engine power output.

Figure 5: Schematic diagram of engine and turbocharger operation

Figure 5: Schematic diagram of engine and turbocharger operation

Source: Lycoming Operator’s Manual, annotated by the ATSB

Maintenance history

As part of the investigation, the ATSB requested the maintenance logs and component log cards for the aircraft. Although the provided information was incomplete, the maintenance history was able to be inferred from the supplied documents as follows:

  • Lycoming engine TVO‑435, S/N: L‑751‑52 was installed February 2000 at 6,752 airframe hours. The engine component control card showed a number of zero‑hour components at the time of engine installation, indicating that this engine was likely either a new or overhauled unit. Lycoming Service Instruction No. 1009BE specified a 12‑year, 1,000 hour time between overhauls (TBO). This interval was correctly annotated in the engine log card.
  • The engine was removed on 24 February 2014 (+14 years) at 7,088 airframe hours (+336 engine hours), and was bulk stripped in lieu of being overhauled, to satisfy the requirements of CASA air worthiness bulletin (AWB) 85‑5 Issue 1.[7] The same engine was refitted on 20 March 2014.

The information supplied to the ATSB showed that prior to November 2022, the aircraft flew only limited hours, having recorded 425 airframe hours in 22 years (at an average of 19.3 hours/year). Depending on how these hours were flown, the aircraft may have required special maintenance actions and/or storage procedures. If these actions were not taken, corrosion, or contamination of components may affect serviceability. No record of storage or preservation penalty maintenance was identified in the provided records. 

Autorotation

When an engine failure occurs in a single‑engine helicopter such as the Kawasaki 47GB3‑KH4, the pilot must immediately lower the collective and enter autorotation to reduce rotor drag sufficiently to maintain normal rotor RPM. This is a power‑off manoeuvre wherein the engine is disengaged from the main rotor and the rotor blades are driven solely by the upward flow of air through the rotor during descent. The most common reasons for an autorotation are an engine or drive system failure. If the engine fails, the freewheeling unit[8] automatically disengages the engine from the main rotor, allowing it to rotate freely. The tail rotor, still driven by the main rotor transmission, continues to provide yaw control via the anti‑torque pedals.

The United States Federal Aviation Administration Helicopter Flying Handbook noted that the rate of descent during autorotation is influenced by various factors, including:

  • bank angle
  • density altitude
  • gross weight
  • main rotor RPM
  • trim condition
  • airspeed.

Pilots control the autorotative descent rate using airspeed and main rotor RPM. Airspeed is managed with the cyclic[9] pitch control, similar to normal powered flight. The descent angle can range from vertical to a minimum angle for maximum horizontal range. The rate of descent is highest at zero airspeed, reaches its minimum at approximately 50‍–‍60 kts (depending on the helicopter and conditions), and increases again at higher speeds.

During an autorotative landing, the kinetic energy associated with the helicopter’s airspeed and rotating main rotor blades are used to arrest the descent and cushion the landing. Termination of the autorotation usually involves initially flaring the helicopter to reduce the airspeed, rate of descent and, if necessary, increase the rotor RPM. The degree of flare effect is influenced by both the airspeed at the time aft cyclic is applied, as well as the rate of cyclic application.

Autorotative terminations at very low airspeeds are more challenging than those performed at the minimum rate of descent airspeed as they offer minimal flare effect. In that case, cushioning the landing using the stored rotor energy requires more precise collective application.

The Kawasaki 47G3B-KH4 flight manual stated that, in the case of an engine failure, the pilot must:  

execute a normal autorotative descent and establish a level attitude prior to ground contact. At a height of approximately 10 feet above the ground, apply collective pitch in sufficient quantity to stop descent as ground contact is made. The best descent speed is 55 mph [48 kt].

Meteorological information

At the time of incident, visibility was in excess of 10 km, with scattered cloud[10] well above the aircraft operating height, no precipitation and an east‑south‑easterly wind at 11 kt.

The meteorological conditions reported by the pilot at the time of incident were consistent with the Bureau of Meteorology observations, which recorded a temperature of 36°C and dew point[11] of 11°C at the incident location. 

The process of vaporising fuel in a carburetted engine can cool the airflow sufficiently to permit ice formation in the carburettor throat that restricts airflow to the engine. According to the Civil Aviation Safety Authority Carburettor icing probability chart, the probability of carburettor icing, based on the prevalent temperature and dewpoint at Katherine Gorge was on the outer limit of the ‘light icing – cruise or descent power’ zone. Of note however, the turbocharger compressor used in the Kawasaki 47G3B‑KH4 heats the inlet air to the carburettor, significantly reducing the potential for carburettor icing. 

Operating weight

The passenger manifest completed by the pilot prior to take‑off recorded the empty weight of the aircraft, the pilot and both passengers, plus fuel. An allowance of 100 kg was made for the weight of fuel. The passenger weights were only verbally requested, and not physically checked by the pilot. However, the calculated total take‑off weight was well below the maximum take‑off weight so any inaccuracy in passenger weights was unlikely to have resulted in the aircraft being overloaded. 

Aircraft fuel 

The operator conducted an examination of the fuel in the aircraft following the incident and reported to the ATSB that there was adequate fuel remaining in the tank. 

The operator also stated that the aircraft had been refuelled with premium 130 octane fuel by the pilot prior to take‑off, and that a post‑incident examination of the fuel quality did not reveal any signs of contamination or leakage.

Engine examination

Following the incident, the operator started the Lycoming TVO‑435 engine and observed that the wastegate did not operate. Thereafter, they removed the engine and delivered it to a third‍ party maintenance facility for examination. As depicted in Figure 6, the post‑incident inspection of the engine revealed the presence of an approximately 6.5 cm crack on the right exhaust collector, with no other defects identified. 

The exhaust system of the aircraft engine attains extremely high operating temperatures. The consequent widening of the crack due to heat expansion would result in the escape of exhaust gases from the defective section, resulting in inadequate drive pressure for the turbocharger compressor and reduced power output. Information provided by the engine manufacturer supported that conclusion. As such, exhaust gas bleed from the crack before the turbocharger resulted in the wastegate remaining closed. 

The ATSB did not undertake a metallurgical analysis of the exhaust pipe, however, exhaust systems are generally prone to metal fatigue over time due to continuous vibration under corrosive conditions and a cyclical pattern of constant heating and cooling with extreme thermal fluctuations.[12]

While it could not be established when the exhaust crack occurred, the maintenance facility that conducted the post‑accident engine examination assessed that, based on the location and appearance of the defect, it was likely not impact‑related. They further stated that, as the helicopter did not have an engine cowl, the leaking exhaust gases would not have left a residue. This would have made the crack more difficult to detect during a pre‑flight inspection when the engine was cold.

Figure 6: Cracked exhaust collector pipe

Figure 6: Cracked exhaust collector pipe

Source: the maintenance facility that conducted the engine strip down inspection, annotated by the ATSB

Safety analysis

Engine power reduction

The sequence of events described by the pilot and passengers were consistent with a loss of aircraft engine power during flight, necessitating an emergency landing. The ATSB considered the following potential reasons for the reduction in engine power:

  • weather conditions, including carburettor icing
  • fuel contamination or starvation
  • handling‑related issues
  • engine and/or associated systems defect. 

The evidence gathered by the ATSB during the investigation indicated that the 3 initial possibilities were unlikely. 

However, based on information from the engine manufacturer and the personnel that conducted the post‑accident engine examination, a pre‑existing crack in the exhaust collector likely reduced the engine power output during the flight. 

Helicopter maintenance

The ATSB identified that low utilisation of the helicopter may have required special maintenance actions and/or storage procedures to be undertaken to prevent component corrosion or contamination. While there was no evidence that such maintenance was undertaken, it was not possible to determine whether its absence contributed to the crack in the exhaust system. 

Autorotation

Analysis of flight data identified that the helicopter was over inhospitable terrain at the time of the power loss. After turning towards a suitable landing site, the pilot commenced an autorotation to that location. The helicopter proceeded downwind, initially attaining a maximum airspeed of about 70 kt. The airspeed was then reduced to close to the target minimum rate of descent airspeed of 48 kt, providing good potential flare effect to both slow the helicopter prior to touchdown and increase the rotor RPM if necessary.

Despite that, the pilot reported there was minimal flare effect when they approached the landing site, likely due to low rotor RPM. As a result, the pilot was unable to prevent the helicopter colliding with terrain during the termination. Importantly however, none of the occupants were injured.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving Kawasaki 47G, VH‑BEU, 24 km north of Katherine Tindal Airport, Northern Territory on 11 September 2024. 

Contributing factors

  • The right exhaust collector was found to have developed a significant crack, which likely resulted in engine power loss during flight.
  • The pilot was unable to cushion the landing during termination of the autorotation, likely due to low rotor RPM, resulting in the helicopter colliding with terrain.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilot and passengers of the accident flight
  • the operator
  • the maintainer for VH-BEU
  • Civil Aviation Safety Authority
  • accident witness
  • OzRunways data from the pilot’s iPad
  • Bureau of Meteorology
  • Kawasaki Heavy Industries
  • the maintenance facility that conducted the post‑accident engine examination.  

References

U.S. Department of Transportation Federal Aviation Administration Helicopter Flying Handbook, FAA‑H‑8083‑21B (2019).

Lycoming Service Instruction No. 1009BE (2020).

Reciprocating engine and exhaust vibration and temperature levels in general aviation aircraft, U.S. Department of Transportation Federal Aviation Administration (1968).

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the pilot of the accident flight
  • the operator
  • the maintainer for VH‑BEU
  • Civil Aviation Safety Authority
  • Kawasaki Heavy Industries
  • Textron Lycoming
  • United States National Transportation Safety Board
  • Japan Transport Safety Bureau

Submissions were received from:

  • the pilot of the accident flight
  • the operator
  • Civil Aviation Safety Authority

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

[1]      The flat pitch is the power it takes to run the helicopter at 100% rotor RPM on the ground with the collective lever fully lowered. A helicopter flat pitch check is performed pre‑flight to identify any engine performance trends by monitoring manifold pressure. 

[2]      Flying neighbourly is a concept aimed at minimising the noise impact of helicopter operations on local communities.

[3]      Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.

[4]      The term used to describe the position of the 2 needles on the combined engine/rotor tachometer when the 2 needles are not superimposed. When a helicopter enters autorotation, either due to an engine failure or during practice, the needles split as the rotor system drive disengages from the engine. This indicates that the main rotor is no longer being powered by the engine and is instead being driven by the upward airflow through the rotor disc.

[5]      MAYDAY: an internationally recognised radio call announcing a distress condition where an aircraft or its occupants are being threatened by serious and/or imminent danger and the flight crew require immediate assistance.

[6]      ICUS (In Command Under Supervision) operations enable pilots having the relevant aircraft type endorsement to gain command experience and accumulate flight hours when performing pilot‑in‑command duties under supervision.

[7]      The AWB provided guidance on engine bulk strip for the purpose of extending calendar life, in instances where engine calendar life limit was reached before reaching the hourly TBO.

[8]      The freewheeling unit is a mechanism that automatically disengages the engine from the main rotor when engine RPM falls below rotor RPM, allowing continued rotor rotation during autorotation.

[9]      Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.

[10]    Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – scattered indicates cloud covering between a quarter and a half of the sky.

[11]    Dewpoint: the temperature at which water vapour in the air starts to condense as the air cools. It is used, among other things, to predict the probability of aircraft carburettor icing or the likelihood of fog.

[12]    US Department of Transport FAA Report No. NA‑68‑27.

Occurrence summary

Investigation number AO-2024-050
Occurrence date 11/09/2024
Location 24 km north of Katherine Tindal Airport
State Northern Territory
Report release date 09/05/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Engine failure or malfunction, Forced/precautionary landing
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Kawasaki Heavy Industries
Model 47G3B-KH4
Registration VH-BEU
Serial number 2149
Aircraft operator Agri-Muster Pty Ltd
Sector Helicopter
Operation type Part 133 Air transport operations - rotorcraft
Departure point Katherine, Northern Territory
Destination Katherine, Northern Territory
Damage Substantial

Helicopter rotor wash resulting in collision with terrain involving Aerochute Industries Dual, Ingham Airport, Queensland on 7 June 2024

Occurrence Briefs are concise reports that detail the facts surrounding a transport safety occurrence, as received in the initial notification and any follow-up enquiries. They provide an opportunity to share safety messages in the absence of an investigation. Because occurrence briefs are not investigations under the Transport Safety Investigation Act 2003, the information in them is de-identified. 

What happened

On the morning of 7 June 2024, a Recreational Aviation Australia Inc. registered Aerochute powered parachute was being prepared for departure at Ingham Airport, Queensland. The pilot was conducting launch preparations with the assistance of 2 ground crew, positioned at either end of the ground‑deployed parachute. The Aerochute was intending to conduct take-off on the airport apron, away from the main runway. While the pilot was leaning over the front of the parachute, preparing radio and navigation equipment, a Robinson R44 helicopter approached from the north-west down the taxiway for landing on the apron about 40–50 m from the Aerochute (Figure 1). The helicopter downdraft caused the parachute to escape from the ground handlers and inflate suddenly. The sudden inflation of the parachute rocked the Aerochute backwards, ejecting the pilot. The pilot impacted the ground and sustained significant head, neck and rib injuries. 

Figure 1: Terminal area locations of aircraft

Figure 1: Terminal area locations of aircraft

Source: Google Earth with ATSB annotations

Safety message

Helicopter pilots are reminded of the need to be cautious of their rotor wash when operating near persons and aircraft, especially when downwash (rotor wash) effects could cause unintended movement or pose a hazard. Maintaining a minimum safe distance when hovering or taxiing is crucial. CASA AC 91-29 v1.3 advises that light helicopters should observe a minimum 30 metre downwash safety distance, while medium helicopters should maintain a 50 metre distance, and heavy helicopters should keep a 65 metre distance. Being aware of downwash effects and establishing appropriate safety distances around the operating site can help mitigate hazards. 

It is essential that all pilots assess the suitability of areas designated for take-off and landing.  Powered parachute pilots should ensure permission to operate from areas not within the runway surface area and be familiar with local requirements, procedures, and operations. 

Additionally, aerodrome operators should clearly define areas of operations for non-traditional aviation operations when granting permission to operate. 

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, no investigation has been conducted and the ATSB did not verify the accuracy of the information. A brief description has been written using information supplied in the notification and any follow-up information in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions. 

Occurrence summary

Mode of transport Aviation
Occurrence ID AB-2024-032
Occurrence date 07/06/2024
Location Ingham Airport
State Queensland
Occurrence class Accident
Aviation occurrence category Collision with terrain
Highest injury level None
Brief release date 26/08/2024

Aircraft details

Manufacturer Robinson Helicopter Co
Model R44 II
Sector Helicopter
Operation type Part 133 Air transport operations - rotorcraft
Departure point Ingham Airport, Queensland
Destination Ingham Airport, Queensland
Damage Nil

Aircraft details

Model Aerochute Industries Dual
Sector Sport and recreational
Operation type Part 91 General operating and flight rules
Departure point Ingham Airport, Queensland
Destination Ingham Airport, Queensland
Damage Substantial

Collision with building involving Robinson R44 II, VH-ERH, Cairns, Queensland, on 12 August 2024

Final report

Report release date: 10/10/2024

Executive summary

What happened

At about 0151 on 12 August 2024, a Robinson R44, registered VH‑ERH, collided with the top of a 7-storey hotel building in Cairns, Queensland after flying for several minutes below 500 ft around the city. The pilot was fatally injured, the helicopter was destroyed, and the building was damaged. None of the occupants of the hotel were injured. A post-impact fire developed which was contained on the roof of the hotel before being extinguished.

What the ATSB found

There were no airworthiness factors with the helicopter that likely contributed to the accident.

The flight was not authorised, and the pilot was not approved to fly the operator’s helicopters. The pilot had access to the operator’s premises at the airport as they were employed by the operator as a ground crew member. 

The pilot was affected by a significant amount of alcohol before and during the flight, and further increased risk to themselves and those on the ground by conducting the unauthorised flight well below the 1,000 ft allowed for flight over a built-up area. 

The ATSB concluded that, for reasons unknown, pilot actions resulted in a collision with a building while conducting an unauthorised and unnecessary flight, while affected by alcohol, late at night and at low heights over a built-up area, and without night flying endorsements.

Summary video


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

At about 0151 on 12 August 2024, a Robinson R44, registered VH‑ERH, collided with the top of a 7-storey hotel building in Cairns, Queensland. The pilot was fatally injured, the helicopter was destroyed, and the building was damaged. None of the occupants of the hotel were injured. A post-impact fire developed which was contained on the roof of the hotel before being extinguished.

The operator, Nautilus Aviation, reported that the flight was not authorised, and that the pilot was not approved to fly the operator’s helicopters.

Prior to the accident, on the evening of 11 August, the pilot had been socialising with friends at various venues in Cairns. Witnesses reported and video recordings showed that the pilot had been consuming alcohol and that they returned to their apartment around 2300. Video recording from the apartment carpark showed the pilot making their way to a vehicle at 0109 on 12 August and driving away.

A video recording from a Nautilus Aviation hangar at Cairns Airport showed that at 0131 the pilot used ground wheels[1] to position one of the operator’s Robinson R44 Raven II helicopters, registered VH-ERH, onto a helipad. The pilot had access to the premises as they were employed by the operator as a ground crew member (see Pilot information). 

After removing the ground wheels and storing them clear of the helipad, the pilot entered the helicopter at 0134:51 and closed the door. At 0135:47 lighting in the cockpit illuminated, and the helicopter’s strobe lights began to flash. This was likely the time that the pilot selected the helicopter’s battery switch.[2] The strobe lights continued to flash until 0137:23. At the same time the strobes stopped flashing, the lighting in the cockpit also darkened.

Lighting in the cockpit illuminated again at 0137:51, however on this occasion the strobe lights did not flash. The lighting in the cockpit darkened and illuminated 3 more times until 0144:06. The main rotor began to rotate 8 seconds later and at 0146:50 the helicopter lifted off the helipad, turned to the left and headed south towards the Cairns city centre.

Position data (Figure 1) from an onboard global positioning system (GPS, see Recorded data) showed the helicopter tracking along a highway towards the city, before making a slight turn to a new track that corresponded with the location of the pilot’s shared apartment. The helicopter then turned to the right and tracked directly to the northern end of the Cairns wharf complex. The helicopter orbited the complex then headed north towards the Cairns marina and continued along the coastline. Recorded data from the GPS ended about 70 seconds prior to the collision.[3]

Figure 1: Flightpath of VH-ERH

Figure 1: Flightpath of VH-ERH

Image source: Google Earth, annotated by the ATSB.

Ground-based radar data recorded by Airservices Australia (see Recorded data) showed the helicopter’s track crossing from the coastline and flying over the pilot’s apartment a second time. The helicopter circled back towards the coastline, following it for about 1 km before crossing the coastline again. The helicopter’s altitude did not exceed 500 ft throughout the flight.

Two security cameras recorded very brief portions of the final part of the flight (Figure 2). These show the helicopter pitching up, then almost immediately descending steeply before colliding into the roof of the hotel at about 0151:31. 

Figure 2: VH-ERH final flightpath and collision with building

Figure 2: VH-ERH final flightpath and collision with building

Image source: Google Earth, annotated by the ATSB.

The distribution of the wreckage and impact marks (including the main rotor impact marks underneath the accident site) indicated that the helicopter was inverted at impact (Figure 3). Most of the helicopter, including its skids, came to rest on the hotel roof and was destroyed by impact forces and a fuel-fed post-impact fire.

Figure 3: Impact location and hotel room damage

Figure 3: Impact location and hotel room damage

Image source: Queensland Police, annotated by the ATSB.

Parts of the main rotor were found in the rooms underneath the accident site. The helicopter instrument panel, glareshield-mounted GPS, mast, main rotor head and blades were separated from the helicopter’s fuselage during the accident sequence. They were located within the hotel grounds below the impact location. The remaining portion of the rotor blade that impacted the windows was found in parkland across the road from the hotel (Figure 4).

Figure 4: Accident site and wreckage distribution

Figure 4: Accident site and wreckage distribution

Note: Image captured 2022. Image source: Google Earth, annotated by the ATSB.

Context

Pilot information

Experience and qualifications

The pilot was a New Zealand citizen and held a New Zealand Civil Aviation Authority (CAA) commercial pilot licence (helicopter). This licence carried a limitation for night flights to be conducted within 25 NM of a lit aerodrome. The pilot held New Zealand CAA type ratings for Cabri G2 and Robinson R44 helicopters, and a sling endorsement.

The pilot had accumulated 157.8 hours total aeronautical experience, 16.8 hours of which were flown in Robinson R44 helicopters, and 10.35 of which were flown at night in Cabri G2 helicopters. The last flight recorded in the pilot’s logbook was on 29 February 2024 in New Zealand.

In February 2023, the pilot registered for an equivalent Civil Aviation Safety Authority (CASA) flight crew licence in accordance with the Trans-Tasman Mutual Recognition Act 1997. They were granted a Civil Aviation Safety Regulation Part 61 commercial pilot licence (helicopter) in March 2023 with a class rating for single-engine helicopters. The pilot held a CASA helicopter low-level rating and a sling endorsement but did not hold a night VFR rating. There were no entries in the pilot’s logbook to indicate they had previously flown a helicopter in Australia.

Employment with the helicopter operator

The pilot was employed by the operator, Nautilus Aviation, as a ground crew member in April 2024. Their duties included taking fuel by road to the operator’s helipad near the Cairns marina, washing and re-fuelling helicopters, passenger transfer by vehicle, and other general ground duties. On the day of the accident, the pilot was due to travel to Horn Island to commence a new role within the organisation driving a fuel truck and re-fuelling aircraft.

Medical information

The pilot held a valid New Zealand CAA class 2 medical certificate and CASA class 1 and 2 civil aviation medical certificates with no restrictions. Prior to commencing work with the operator, the pilot was required to undertake drug screening and on 26 April 2024, was re-screened as a requirement for their new role within the organisation. The results on both occasions were negative. 

A toxicology report indicated that the pilot had a significant blood alcohol content (BAC). A full drug screen was conducted and no drugs were detected. No significant carbon monoxide was detected (below 5%). A post-mortem examination report was not available at the time of publication.

Minimum height rule

Civil Aviation Safety Regulations 1998, Reg 91.265 (3) requires that, when over populous areas (including a city or a town), the pilot in command of a rotorcraft must fly at least 1,000 ft above the highest feature or obstacle within a 300 m horizontal radius immediately below the helicopter. Limited exceptions to the rule apply for medical transport operations and certain aerial work operations.

Air traffic control

Airservices Australia operates a control tower at Cairns Airport that is staffed 24 hours a day. On the night of the accident there was a single controller on a shift from 2145 to 0530.

Prior to the accident, the controller had handled a flight at around 0030, and they were expecting another flight at about 0500. While there were no scheduled flights between those times, the controller remained available for unscheduled flights such as search and rescue operations or for diverted flights. During this time, the controller completed internal computer-based training courses and clerical tasks.

The controller was able to take rest breaks but remained in the visual control room[4] where they were provided with a lounge chair, television, and basic amenities. While away from their normal workstation, the controller maintained a listening watch for unscheduled flights through speakers in the tower. The controller stated that they did not notice any airport activity outside of the tower.

As there were no scheduled flights, most of the controller’s attention was with equipment inside the control tower, such as the integrated tower automation suite (INTAS) console. At night, a controller would normally be alerted to an aircraft’s presence by:

  • monitoring the displays for the expected appearance of an aircraft based on submitted flight plan data
  • radio communications or radio interference sounds.

There were no other audible or attention-getting alerts to advise controllers to aircraft becoming active in the controller’s airspace; rather, an aircraft symbol would appear on the console display. In this case, the helicopter would have been visible on the console from 0144:28.

The controller recalled that they heard unexpected radio interference sounds on multiple occasions and checked the INTAS console for any new flight plans that may have appeared in the system. Recorded INTAS data shows the controller interacting with it at 0143:11 which was around the time the accident flight helicopter was being started.

Airside access and security

As an employee of the operator, the pilot had security code access to the building and was able to make their way to the hangar. In addition to VH-ERH, there were 2 larger helicopters in the hangar and their overall length prevented the hangar doors from being closed. The pilot was able to remove the helicopter from the hangar and position it on a helipad. To start the engine of a Robinson R44, a key is used to select both magnetos,[5] and the engine starter is engaged by pushing a button on the collective.[6] The operator stated that it was normal practice to leave keys in helicopters that were positioned in their hangars.

Operators such as Nautilus Aviation were required to be compliant with the North Queensland Airports (NQA)[7] transport security program. This required unattended aircraft positioned airside to be secured. This could be achieved by removing keys from keyed ignitions, not storing keys in the aircraft, locking doors, and other methods such as storing aircraft in locked or secured hangars.

There were Australian Federal Police officers and airport safety officers on duty at the time the pilot was preparing the helicopter, but they were not in the vicinity of the hangar. Additionally, by the pilot turning off the helicopter’s strobe lights, there would have been no visual cues to attract the attention of these officers.

Aircraft information

The helicopter was a Robinson R44 Raven II, serial number 12465, manufactured in the United States in 2008 and first registered in Australia on 29 October 2008. It was issued with a certificate of airworthiness in the normal category on 14 November 2008. The helicopter was registered with Nautilus Aviation on 13 August 2014.

A periodic inspection and other maintenance tasks were carried out on 7 August 2024. At the time of the accident, the helicopter had accumulated 4,142 flying hours.

The R44 is a single-engine, light utility and training helicopter with a semi-rigid, two-bladed main rotor, a two-bladed tail rotor and skid type landing gear. It has an enclosed cabin with two rows of side-by-side seating for a pilot and three passengers.

Meteorological information

Light drizzle with visibility to the Cairns airport terminal 1.5 km away could be seen on a video recording from the operator’s hangar when the pilot arrived at 0131. The drizzle had increased to a point where the terminal was less visible by time the pilot took-off at 0146:50.

While the flight was conducted at night, this would not have affected visibility for the pilot as there was an abundance of artificial lighting from city buildings and street lighting.

Recorded data

The helicopter was fitted with a Garmin aera 660 GPS, from which position and altitude data from the accident flight was successfully recovered at the ATSB’s technical facility in Canberra. 

Airservices Australia provided ground-based radar data for the accident flight. This data combined primary surveillance radar (PSR) and secondary surveillance radar (SSR) data into a single, smoothed track.

The helicopter was not fitted with a cockpit voice recorder or flight data recorder, and due to the size of the aircraft, was not required to be.

Wreckage information

The ATSB conducted a basic examination of the helicopter wreckage on the hotel roof and within the hotel grounds. The helicopter was subsequently transported to a secure facility where a detailed examination was carried out (Figure 5).

Figure 5: Examination of wreckage

Figure 5: Examination of wreckage

Image source: ATSB.

The helicopter’s cockpit, systems and engine were severely damaged by the impact and post‑impact fire. Within the limitations of the available evidence, there were no indications of in‑flight fire or defects.

  • The absence of noteworthy damage to the helicopter’s skids indicated that the helicopter did not impact the hotel roof in an upright position.
  • There was no evidence of the main rotor contacting the tail boom, which remained intact.
  • Marks on one of the engine oil coolers indicated that the engine and ring gear were rotating at the time of impact.
  • Where possible, continuity was established with the main rotor, tail rotor drives and flight controls.
  • Main rotor blade damage was indicative of the engine driving the main rotors at a high-power setting.
  • The helicopter was fitted with bladder fuel tanks, which were breached during the accident sequence, but it was not possible to assess how the tanks were breached.

A rotor blade tip shattered the window of the room underneath the accident site (Figure 6), and a section from the same rotor blade destroyed the window of an adjacent room (Figure 7).

Figure 6: Hotel room damage

Figure 6: Hotel room damage

Image source: ATSB.

Figure 7: Hotel adjacent room damage

Figure 7: Hotel adjacent room damage

Image source: ATSB.

Safety analysis

The flight was an unauthorised but purposeful act, however the ATSB did not determine the reason the pilot elected to conduct the flight. The ATSB can conclude from the available evidence that there were no airworthiness factors with the helicopter that likely contributed to the accident. 

The Civil Aviation Safety Authority has put in place regulations designed to ensure the safety of flight. The pilot was affected by a significant amount of alcohol before and during the flight. The pilot further increased risk to themselves and those on the ground by conducting the unauthorised flight well below the 1,000 ft allowed for flight over a built-up area. 

While the pilot held a helicopter commercial pilot licence and had experience flying the Robinson R44, the pilot was not approved to fly the operator’s helicopters at any time. Additionally, the pilot did not hold the appropriate rating to fly helicopters at night and had never flown a Robinson R44 at night. 

Aviation transport security regulations are in place to keep unauthorised persons out of airports. However, as a ground crew of the operator, the pilot was authorised to have access to the helicopter at Cairns Airport and took advantage of that access. Further, based on the strobe lights being turned off, it was apparent that the pilot was wanting to conceal the departure from the airport from air traffic control and airport staff.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following finding is made with respect to the collision with building involving Robinson R44 II, VH-ERH, Cairns, Queensland on 12 August 2024. 

Contributing factors

  • For reasons unknown, pilot actions resulted in a collision with a building while conducting an unauthorised and unnecessary flight, while affected by alcohol, late at night and at low heights over a built-up area, and without night flying endorsements.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2024

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Robinson R44 helicopters can be manoeuvred (such as in and out of hangars) by detachable ‘ground wheels’ temporarily fitted to the helicopter’s skids.

[2]     The operator reported that it was normal practice for the strobe lights to remain selected on at all times and not selected off post-flight. The strobe lights would flash immediately after the battery switch was selected on.

[3]     This is consistent with Garmin aera 660 units previously recovered from accident sites.

[4]     The top floor of the control tower from which the airport can be seen.

[5]     A magneto is a device that provides a self-generated charge to the spark plugs of a piston engine.

[6]     A collective is a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.

[7]     North Queensland Airports is a group comprised of Cairns Airport, Mackay Airport and Mackay Airport Hotel.

Occurrence summary

Investigation number AO-2024-046
Occurrence date 12/08/2024
Location 4 km from Cairns Airport
State Queensland
Report release date 10/10/2024
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Robinson Helicopter Co
Model R44 II
Registration VH-ERH
Serial number 12465
Sector Helicopter
Departure point Cairns Airport
Damage Destroyed

Accredited Representative to the Civil Aviation Authority of Vanuatu investigation – Collision with terrain involving Britten-Norman BN2A-20, YJ-AT2, near Port Vila, Vanuatu, on 15 July 2024

Summary

The Civil Aviation Authority of Vanuatu (CAAV) investigated a fuel starvation and collision with terrain accident involving Britten-Norman Islander BN2A-20, YJ-AT2, 6 km east-south-east of Port Vila International Airport, Vanuatu, on 15 July 2024. The CAAV requested assistance from the Australian Government represented by the ATSB.

To facilitate this support and to provide the appropriate protections for the information, the ATSB appointed an accredited representative in accordance with paragraph 5.23 of the International Civil Aviation Organization Annex 13 and commenced an investigation under the Australian Transport Safety Investigation Act 2003.

On 14 August 2025, the CAAV released its final report into this accident. This report is available here.

Any enquiries relating to the investigation should be directed to the CAAV.

Occurrence summary

Investigation number AA-2024-008
Occurrence date 15/07/2024
Location near Port Vila, Vanuatu
State International
Report status Final
Investigation type Accredited Representative
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Highest injury level Fatal

Aircraft details

Manufacturer Britten Norman
Model BN2A-20
Registration YJ-AT2
Aircraft operator Air Taxi Vanuatu
Sector Piston
Damage Destroyed

Wirestrike and collision with terrain involving Air Tractor AT-502, VH-CJY, 19 km south-east of Lake Cargelligo Airport, New South Wales, on 18 July 2024

Summary

The ATSB is investigating a wirestrike and collision with terrain involving an Air Tractor AT-502, registration VH‑CJY, 19 km south-east of Lake Cargelligo Airport, New South Wales, on 18 July 2024.

During aerial agricultural spraying operations, the aircraft struck a wire and subsequently collided with terrain resulting in substantial damage. The pilot was fatally injured.

The ATSB deployed a team of transport safety investigators to the accident site with experience in aircraft operations, engineering, and human factors. As part of the on-site phase of the investigation, ATSB investigators examined the aircraft wreckage and other information from the accident site, interviewed witnesses and any involved parties, and examined maintenance records and any recorded data.

The draft report internal review process has been completed. The draft report has been distributed to directly involved parties (DIPs) to check factual accuracy and ensure natural justice. Any submissions from those parties will be reviewed and, where considered appropriate, the draft report will be amended accordingly.

Following the external review process, any submissions and amendments to the draft report are internally reviewed. Once approved, the final report is prepared for publication and dissemination and released to DIPs prior to its public release. 

The final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties, so that appropriate safety action can be taken.

Last updated:

Occurrence summary

Investigation number AO-2024-042
Occurrence date 18/07/2024
Occurrence time and timezone 12:56 Australian Eastern Standard Time
Location 19 km south-east of Lake Cargelligo Airport
State New South Wales
Report status Pending
Anticipated completion Q4 2026
Investigation level Defined
Investigation type Occurrence Investigation
Investigation phase Final report: External review
Investigation status Active
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Wirestrike
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Air Tractor Inc
Model AT-502
Registration VH-CJY
Serial number 502-0093
Aircraft operator Thomson Airborne Pty Ltd
Sector Turboprop
Operation type Part 137 Aerial application operations
Activity General aviation / Recreational-Aerial work-Agricultural spreading / spraying
Departure point Lake Cargelligo Airport, New South Wales
Destination Lake Cargelligo Airport, New South Wales
Injuries Crew - 1 (fatal)
Damage Destroyed

Collision with terrain involving Cessna 172N, VH-SQO, near Mulgathing, South Australia, on 27 June 2024

Final report

Report release date: 01/05/2025

Investigation summary

What happened

On the morning of 27 June 2024, the pilot of a Cessna Aircraft Company 172N, registered VH‑SQO, was assisting with mustering sheep at Mulgathing Station, South Australia. At about 0810 local time, a witness on a motorbike about 500 m away observed the aircraft dive down on what they presumed was a flock of sheep to an estimated height of about 50 ft above the ground before climbing rapidly, turning to the left and then descending towards the ground. The aircraft was destroyed, and the pilot who was the sole occupant was fatally injured.

What the ATSB found

The ATSB found that, while mustering sheep without the appropriate endorsement to do so, the pilot lost control of the aircraft leading to an aerodynamic stall and spin from an altitude that was not recoverable. Although not contributory, it was also found that the upper torso restraint part of the lap-sash seatbelt was not worn at the time of the accident. Further, the pilot was hired for a job advertised as aerial stock mustering but did not require an aerial mustering endorsement as the operator’s intention was that the role only involved aerial spotting. 

What has been done as a result

The operator has advised that it is preparing a Safe Aerial Spotting & General Station Aviation Manual. It has also implemented a pilot mentoring program and initiated a third-party safety audit. It is also undertaking a review of its operations to ensure compliance with the Civil Aviation Safety Authority regulations as well as the safety and training standards for pilots. 

Safety message

This accident highlights the importance of managing airspeed and bank angle to minimise the risk of an aerodynamic stall. This is particularly important when operating in close proximity to the ground, such as during take-off, landing and when conducing low-level air work, as recovery may not be possible. Low-level flying is a higher risk activity and mustering at low-level adds additional complexity and risk. It is important that pilots operate within the boundaries of their training and qualifications to ensure an adequate margin of safety is maintained.

Safety Watch logo

The ATSB’s SafetyWatch initiative highlights broad safety concerns generated by its investigation findings, and from  occurrence data reported by industry. One of the safety concerns is Reducing the severity of injuries in accidents involving small aircraft, which includes the appropriate fitment and use of seatbelts. This SafetyWatch notes that in several of its investigations, the ATSB has found injuries to aircraft occupants may have been avoided, or made less severe, through the appropriate use of multi-point harnesses.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On the morning of 27 June 2024, the pilot of a Cessna Aircraft Company 172N, registered VH‑SQO, met co-workers for breakfast at about 0630 local time before a morning briefing on the task for the day, which involved mustering sheep at Mulgathing Station (owned by Jumbuck Pastoral (operator)), South Australia. At about 0700, the station manager, assistant manager and 4 station hands set off for a yard about 30 km south-east of the homestead (Figure 1). Meanwhile, the pilot drove to the airstrip about 5 minutes away, took off and flew towards the yard to rendezvous with the other workers. 

The station manager and 4 station hands were marking[1] lambs in the yard while the pilot, in the aircraft, and the assistant manager (witness) on a motorbike, were rounding up stray sheep. At about 0810, the witness observed the aircraft flying overhead at about 300 ft above ground level looking for sheep when the pilot radioed to say they had found 2 flocks about 2 km away. The witness converged on one flock and observed the aircraft circling about 500 m away over what was presumed to be the second flock. 

The witness radioed the pilot to ask if they needed help moving the sheep. The pilot responded that they thought they would be able to do it with the aircraft. The aircraft was then observed to continue circling to the left at a height the witness estimated to be 150‍–‍200 ft before diving at an angle of about 45° towards what was presumed to be the flock of sheep, to a height of about 50 ft. The witness estimated that the aircraft then climbed out at about a 60° nose‑up attitude to a height of about 250‍–‍300 ft, rolled to the left and descended nose-down towards the ground and impacted terrain. No bird activity was noted by the witness and they reported not hearing any changes in the engine noise during the accident sequence. While they were not certain of the actual angle of climb, they noted that it was steeper than the descent. The aircraft was destroyed, and the pilot who was the sole occupant was fatally injured.

Figure 1: Accident location with reference to Coober Pedy and the Stuart Highway

Figure 1: Accident location with reference to Coober Pedy and the Stuart Highway

Source: Google Earth, annotated by the ATSB

Context

Pilot information

The pilot, a New Zealand citizen, held a Civil Aviation Safety Authority Part 61 Commercial Pilot Licence (Aeroplane) with a single and multi-engine class rating with endorsements for retractable undercarriage, manual propeller pitch control, and low‑level and instrument ratings. They did not hold an aeroplane aerial mustering endorsement. The pilot’s commercial licence was issued on 17 August 2023 in accordance with the Trans‑Tasman Mutual Recognition Act 1997. They had recorded 441.5 total flying hours in their logbook, dated 16 June 2024. 

The pilot’s low‑level training was conducted on 1‍–‍3 December 2023 and their low‑level rating was issued on 3 December 2023, which was also their last flight review. The flight test was conducted in a Cessna 172 aircraft, with all elements of the low‑level rating with a single‑engine aeroplane endorsement assessed as satisfactory, including the approach and recovery from a stall in level flight and turning.[2] The instructor who conducted the pilot’s low‑level training noted that the role was for aerial spotting rather than mustering, therefore, the elements for the aerial mustering endorsement were not tested.

The pilot was employed by Jumbuck Pastoral to work at Mulgathing Station in December 2023. The pilot’s logbook showed 70 flights were conducted by the pilot at Mulgathing between January 2024 and the last logbook entry on 16 June 2024. These flights totalled 198.3 hours, all of which were conducted in VH‑SQO.

The pilot held a Class 1 Aviation Medical Certificate with no restrictions, valid to 29 November 2024. The pilot’s aviation medical examination indicated no reported medical conditions nor prescribed medications. Co‑workers reported the pilot was fit, healthy, did not drink alcohol excessively and did not smoke. On the morning of the accident, witnesses stated that the pilot demonstrated no abnormal behaviour.

Aircraft information

VH‑SQO was a Cessna Aircraft Company 172N 4‑seat, single‑engine, high (strut‑braced) wing, all metal, unpressurised, fixed (tricycle) undercarriage aircraft. The aircraft was manufactured in the United States in 1978 and assigned serial number 17270255. It was first registered in Australia on 29 August 1978. The operator had been the registered owner of the aircraft since the date of registry. 

The current maintenance release was issued on 8 March 2024 and was valid until 8 March 2025 or 14,620.8 hours total time‑in‑service, whichever came first. At the time of take‑off for the accident flight, the aircraft had accumulated 14,602.7 hours. The maintenance release showed that required maintenance had been completed and no defects were recorded. 

Meteorological information 

There was no airport forecast for Mulgathing Station, however, the Bureau of Meteorology graphical area forecast issued at 0137 local time and current for the time of the accident forecast no cloud or weather below 5,000 ft and visibility greater than 10 km. This was consistent with witness accounts, which reported that, on the morning of the accident, the weather was fine, clear and the temperature was cool, not cold. No wind or cloud cover was observed, and the conditions were described by a witness as being ‘almost perfect for paddock work’. 

Wreckage and impact information

The ATSB’s onsite examination found that the aircraft impacted with terrain at about a 70° pitch down attitude with undamaged trees behind the wreckage. Ground impact marks were directly under the wreckage indicating no forward momentum. 

The engine was deflected to the right of the longitudinal axis by about 25° (Figure 2). The crank case had fractured in overload, which separated the propeller from the engine. The underside of the left wingtip leading edge exhibited compression damage, which was also evident along the span of the right wing leading edge. The aft fuselage had folded towards the right with compression damage evident on the right side. The flaps were in the full retracted position.

Figure 2: VH-SQO accident site

Figure 2: VH-SQO accident site

Source: ATSB

The aircraft’s flight controls and structure did not identify any pre‑existing faults or pre‑impact defects or failures, and no evidence of a birdstrike was observed. Additionally, one of the propeller blades showed significant rotational abrasion damage and chord-wise twisting indicating that the engine was driving the propeller under significant power at the time of impact. 

Examination of the fuel drum used to refuel the aircraft showed it had a water drain and filter in a clear bowl with uncontaminated fuel evident in the filter bowl. Although the fuel selector was found to be in an undetermined position due to the accident damage, there was a significant amount of fuel remaining in both tanks, a strong smell of fuel around the aircraft, and the fuel tank caps were observed to be locked in place. 

Aerodynamic stall and spin 

A wing generates lift as a result of the pressure differential created by airflow over the wing’s surface. The angle between the incoming or relative air flow and wing chord is known as the angle of attack (AoA). As the AoA increases, lift increases up to a certain angle, known as the critical AoA. At this point, the airflow over the upper surface of the wing becomes separated. This condition is referred to as an aerodynamic stall (or simply a stall) and results in a significant loss of lift and an increase in drag. Due to the sudden reduction in lift from the wing and rearward movement of the centre of lift, typically an uncommanded aircraft nose-down pitch results. Most general aviation aircraft typically have a critical AoA of around 16°. This critical AoA can be exceeded at any airspeed, any (pitch) attitude and any power setting. However, a high AoA combined with a low airspeed most commonly results in a stall condition.

A spin can result when an aircraft simultaneously stalls and yaws.[3] The yaw can be initiated by rudder application (through manipulation of the rudder pedals) or by yaw effects from a range of factors that include aileron deflection, torque and engine/propeller effects. A spin is characterised by the aircraft following a downward, corkscrew path and requires significantly more altitude for recovery compared to a wings level stall (Federal Aviation Administration, 2021).

The Cessna Aircraft Company Pilot’s Operating Handbook stated that the stall recovery height for the Cessna 172N is 180 ft. The handbook also stated that the recovery height for a one‑turn spin is 1,000 ft. 

Wood and Sweginnis (2006), Aircraft Accident Investigation – 2nd edition, provides the following description of the wreckage from an aircraft that had spun into the ground, with reference to Figure 3:

There is little or no evidence of forward motion. Although the fuselage probably impacted at a steep nose down attitude, it is likely that there is evidence of a wing tip striking the ground before the nose. The down-going wing will normally strike the ground before the up-going wing, providing one clue as to the direction of the spin. Both the fuselage and the wings will probably have damage which reflects both a high sink rate and yaw. Tall thin objects on the ground, like trees and fence posts, are likely to penetrate the airplane almost from bottom to top, reflecting the almost vertical trajectory of the airplane. Undamaged objects may be found immediately behind the trailing edges, again indicating the vertical path of the airplane.

Figure 3: Example wreckage pattern from a spin  

Figure 3: Example wreckage pattern from a spin

Source: Wood and Sweginnis (2006)

Aerial mustering operations and observations 

General information

Aerial mustering is defined as the use of an aircraft to locate, direct and concentrate livestock. By definition, it is a hazard‑rich activity due to the inherent characteristics of the operation. Such hazards include manoeuvring at low-level, high workload, negative effects from weather, proximity to obstacles and the division of attention between flying and livestock management (Civil Aviation Safety Authority, 2015). 

In addition to the aviation-specific definition for aerial mustering described above, in general terms, mustering livestock is usually a collaborative activity involving a ground-based team, typically using vehicles such as motorbikes, as well as personnel in the air, in either aeroplanes or rotorcraft. The role of the pilot in the overall mustering team could either be aerial spotting, or aerial mustering. The spotting role would involve the pilot searching for livestock and communicating their location to the ground team for them to round up. This is generally performed at a higher position and does not require the need to perform dynamic aircraft movements. This is somewhat different to aerial mustering, which, as defined by the Civil Aviation Safety Authority, would involve the intentional use of the aircraft to direct or concentrate the livestock. The ratings and endorsements a pilot had would limit which of these activities they could undertake. 

Regulatory requirements

Since the introduction of Civil Aviation Safety Authority Civil Aviation Safety Regulations 1998 Part 61 in September 2014, an aeroplane aerial mustering endorsement was required to muster livestock with an aeroplane in Australia. Furthermore, an applicant for the aeroplane aerial mustering endorsement was required to hold a low-level rating with an aeroplane low-level endorsement. The mustering endorsement had additional elements and performance criteria to the low-level rating, which included demonstrating:

  • handling of the aeroplane up to the limits of the flight-manoeuvring envelope
  • coordinating and conducting an aerial mustering operation
  • an underpinning knowledge of critical operational conditions including aerodynamic stall and the safety hazards and risks of low‑level operations and methods of control. 

To conduct aerial spotting a low‑level endorsement was required.

All aerial work operations in aeroplanes and rotorcraft are covered by Part 138 of the regulations. This includes operations that require an aerial work certificate as well as those that do not. However, if the aerial work is conducted over land owned or occupied by the person who is the registered operator of the aircraft or otherwise the owner of the aircraft, an aerial work certificate is not required. This is known as limited aerial work operations.

VH-SQO was owned by Jumbuck Pastoral and flying operations were conducted over their land. 

Mustering observations

For the duration of the pilot’s time at Mulgathing Station, the pilot was observed by several staff members to have used a ‘dive‑bombing’ technique to muster sheep on multiple occasions. However, all staff members stated that they thought the procedure was normal operations for mustering and that the pilot was qualified to perform the activity. Following the accident, these staff became aware that the pilot was not qualified to conduct these aerial mustering manoeuvres.

Job application and role description

The pilot originally applied for a job with Jumbuck Pastoral at Bulgunnia Station, about 90 km east of Mulgathing. Although that application was not successful, Jumbuck Pastoral subsequently offered the pilot a similar job at Mulgathing Station. The job advertisement described the position as a pilot/station hand, stating that:

Your main duties while flying will be aerial stock mustering and supporting the crew on the ground during musters along with periodical property and stock inspections.

The qualifications required for the role were described as:

• Australian Commercial Pilots License (essential)

• Minimum 200 hours of total flying time (essential)

• Experience flying a Cessna 172 (essential)

• Low-Level Flying Endorsement (can be obtained if successful)

On 13 February 2025, in response to the draft report, the operator advised that the job description for the role involved aerial spotting only, to assist on‑ground mustering teams. It indicated that it had never required its aeroplane pilots to control or manoeuvre livestock directly. Instead, it relied on helicopter pilots for controlling stock movement when motorbikes could not be safely used on the ground for mustering cattle.

The operator also stated that the intention of the role was communicated to the pilot during their engagement with the company and the pilot was provided a copy of the Mulgathing Station Guide, which stated that: 

Our mustering activities are supported by a Cessna 172 plane, with the pilot coordinating the muster below by relaying the location of stock in the paddocks. For those on 2-wheel motorbikes, stock visibility can be limited for a number of reasons, so having a pilot in the air assisting is an enormous help to ensure we muster paddocks cleanly and don’t leave any sheep behind. The terrain around the station can be tricky with a lot of rock, scrub and rough paddocks, so this is an added benefit.

Survival aspects

The aircraft impacted terrain with a 70° nose down attitude, which significantly compressed the liveable space within the cockpit. Injuries observed by first responders were consistent with those typically sustained from an aircraft accident. At the time of publication, the post‑mortem report was pending, however, the toxicology report indicated no presence of alcohol or drugs, and carbon monoxide[4] levels were also indicated to be within the normal range.    

The pilot was not wearing a helmet at the time of the accident, nor were they required to. The pilot seat remained attached to the seat rails and was locked in a mid‑forward position. The pilot’s seat was fitted with a 3‑point lap‑sash belt and shoulder harness (upper torso restraint (UTR)). The pilot’s lap belt was reported to have been removed by the first responder to facilitate the pilot’s removal. The lap belt and clasp remained anchored to the floor and appeared to be in good condition. Inspection of the cockpit revealed that the UTR was stowed in the roof line.

When correctly worn, UTRs form an important part of the occupant protection system in aircraft, and the benefits in reducing the likelihood and severity of injuries is well established. A significant benefit of correctly fitted UTRs is the minimisation of body movement to prevent the body striking the aircraft structure in lateral and longitudinal impacts (Young, 1967). These findings are supported by research conducted by the United States National Transportation Safety Board (NTSB, 2011), which found that pilots who used lap belts only were nearly 50% more likely to be seriously or fatally injured compared with those who wore lap belts with UTRs.

With regards to the requirement for seatbelt usage in Australia, Civil Aviation Safety Authority Civil Aviation Safety Regulations 1998 Part 91.550 stated the following requirements:

• At all times during the flight, such a pilot must occupy a pilot seat, with the seatbelt [lap-sash belt] securely fastened.

• During take-off, landing or any other period that the pilot in command directs, each flight crew member required for the flight must occupy the flight crew member’s crew station with the seatbelt and shoulder harness securely fastened. 

Safety analysis

Introduction

While mustering sheep on Mulgathing Station, South Australia, a Cessna Aircraft Corporation 172N, registered VH-SQO, was observed to dive towards a group of sheep before pulling out of the dive, rolling to the left, descending towards the ground and impacting terrain. 

The wreckage examination found there were no defects or anomalies with the recovered components of the aircraft that might have contributed to the accident and the damage to the propeller indicated a power‑on impact. Additionally, there was no evidence indicating an adverse weather event or fuel issue. Pilot incapacitation was also unlikely given the pilot’s age, medical history, reported health prior to the flight and toxicological results.

This analysis will focus on the examination of the factors that led to the pilot losing control of the aircraft at low-level while attempting to muster sheep. It will also consider the job advertisement for the pilot position and the use of upper torso restraints.

Loss of control

The aircraft was observed diving from about 150‍–‍200 ft to approximately 50 ft above the ground then pitching up at about a 60° nose-up attitude to about 250‍–‍300 ft with no observed change in the engine power setting, before banking to the left and descending to the ground. While there can be limitations to witness recollections, the key points made by the witness were that the angle of climb was steeper than the angle of descent, and that the exit height was greater than the entry. These aspects were consistent with a loss of control during the exit of the dive. The steep climb‑out from the dive likely resulted in a rapid decay of airspeed and increase in the angle of attack that made the aircraft susceptible to a power‑on stall/spin situation. Furthermore, the onsite examination showed that the aircraft impacted terrain in about a 70° nose-down attitude with no forward momentum with both the engine and tail sections deflected to the right. 

Both the observations made by the witness and the condition of the wreckage were consistent with the aircraft stalling and entering a left spin. The Pilot’s Operating Handbook indicated that this occurred at a height from which the stall and spin was not recoverable, resulting in the impact with terrain. 

Pilot qualifications

In order to undertake the activity of aerial mustering with an aeroplane, both a low-level rating and aerial mustering endorsement were required, however, the pilot did not possess the latter. During their time at Mulgathing Station, the pilot was observed on several occasions to dive towards sheep in an attempt to move them. This manoeuvre is considered to be aerial mustering. On the day of the accident, the pilot declined assistance from a colleague on a motorbike, stating their intention to move the sheep with the aircraft and they were subsequently observed conducting this manoeuvre. 

Low-level flying is a higher risk activity and aerial mustering adds further complexity and risk as the pilot must divide their attention between flying the aircraft, monitoring the livestock on the ground and the effects of their flying on the livestock. Not having the additional training and experience that would have come with the aerial mustering endorsement likely left the pilot ill‑equipped to manage the challenges associated with mustering sheep. As they were not instructed in the appropriate techniques for mustering, this placed the pilot at an increased risk of experiencing a loss of control at low-level.  

Job application and role

The pilot applied for, and was awarded, the job described as being a pilot/station hand. The job advertisement stated that the main flying duties would be ‘aerial stock mustering’. As mentioned above, from an aviation perspective this meant that the pilot was required to have an aeroplane aerial mustering endorsement. However, the qualifications specified for the role did not include such an endorsement, nor did the pilot have one. Instead, the qualifications listed were consistent with the operator’s intention for the role of aerial spotting requiring only a low-level rating, which the pilot had. It was unclear to what extent, if any, the description of ‘aerial stock mustering’ influenced the pilot’s actions. 

Despite this, from the time they started the role, up until the day of the accident, they were observed mustering sheep using manoeuvres that were outside the scope of their qualifications and the operator’s intentions. Furthermore, although these actions were witnessed by several staff at the station, including the station manager, none of the staff reported being aware that the pilot was not qualified to perform aerial mustering. 

Seatbelts

The onsite inspection found that the upper torso restraint was stowed in the roof line indicating that it was not used by the pilot. Although the pilot was only required to use the lap belt at the time of the accident, the aircraft was fitted with an over the shoulder sash belt and the benefits of using them are well documented. However, in this case, given the extent of damage to the aircraft, it was unlikely the upper torso restraint would have contributed to the survivability of the accident. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving a Cessna 172N, registered VH‑SQO, near Mulgathing, South Australia, on 27 June 2024. 

Contributing factors

  • While in a steep climb-out after diving towards sheep, control of the aircraft was lost leading to an aerodynamic stall and spin from a height that was not recoverable.
  • Although the pilot held a low-level rating, they were conducting aerial mustering operations without the related qualification. Consequently, the pilot was not appropriately experienced to manage the challenges likely encountered during aerial mustering.

Other factors that increased risk

  • The operator had advertised for a pilot to conduct ‘aerial stock mustering’ operations, but did not require the qualifications to perform that activity as their expectation was that the role would only involve aerial spotting.
  • The upper torso restraint part of the lap-sash seatbelt was not worn on the accident flight.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.

Safety action by Jumbuck Pastoral

On 13 February 2025, Jumbuck Pastoral advised the ATSB that it has undertaken the following safety action:

  • A Safe Aerial Spotting & General Station Aviation Manual is in the process of being prepared.
  • Implemented a mentoring program for pilots, particularly at Mulgathing Station.
  • A safety audit has been conducted by an external third party. This is currently before the Board.
  • It is undertaking a full review of its operations to ensure compliance with the Civil Aviation Regulations 1988 and Civil Aviation Safety Regulations 1998, as well as the safety and training standards for pilots.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • Jumbuck Pastoral
  • Civil Aviation Safety Authority
  • Bureau of Meteorology
  • South Australian Police Service
  • aircraft manufacturer
  • maintenance organisation for VH-SQO
  • accident witnesses.

References

Civil Aviation Safety Authority. (2015). Sector Risk Profile for the aerial mustering sector. https://auntypru.com/wp-content/uploads/2023/11/sector-risk-profile-aerial-mustering-sector.pdf 

Federal Aviation Administration. (2021). Airplane Flying Handbook. (FAA-H-8083-3C). https://www.faa.gov/sites/faa.gov/files/regulations_policies/handbooks_manuals/aviation/airplane_handbook/00_afh_full.pdf

National Transportation Safety Board. (2011). Airbag Performance in General Aviation Restraint Systems (Safety Study, NTSB/SS-11/01). https://www.ntsb.gov/safety/safety-studies/Documents/SS1101.pdf 

Wood and Sweginnis. (2006). Aircraft Accident Investigation – 2nd edition. Endeavour Books.

Young J.W. (1967). A Functional Comparison of Basic Restraint Systems. Federal Aviation Administration, Office of Aviation Medicine (Report No. AM 67-13). https://www.faa.gov/sites/faa.gov/files/data_research/research/med_humanfacs/oamtechreports/AM67-13.pdf 

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • Civil Aviation Safety Authority
  • Jumbuck Pastoral
  • South Australian Police Service
  • maintenance organisation for VH-SQO
  • accident witnesses.

Submissions were received from:

  • Civil Aviation Safety Authority
  • Jumbuck Pastoral
  • South Australian Police Service.

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2025

Title: Creative Commons BY - Description: Creative Commons BY

 Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Lamb marking refers to husbandry procedures including tail docking, castration of males, ear tagging, mulesing, and vaccination.

[2]      For training purposes, these manoeuvres were performed above 3,000 ft.

[3]      Yaw: the motion of an aircraft about its vertical or normal axis.

[4]      Carbon monoxide is a colourless, odourless, tasteless, and poisonous gas that is produced as a by-product of burnt fuel. Exposure to a leak from the exhaust of an aircraft engine into the cabin can lead to elevated levels of carbon monoxide, which can impair cognitive function.

Preliminary report

Report release date: 18/09/2024

This preliminary report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003. 

The occurrence

On the morning of 27 June 2024, the pilot of a Cessna Aircraft Company 172N, registered VH‑SQO, commenced sheep spotting operations at Mulgathing Station, South Australia (Figure 1). At about 0810 local time, a witness on a motorbike about 500 m away observed the aircraft dive down on what they presumed was a mob of sheep to an altitude of about 50 ft above the ground before climbing rapidly, turning to the left and then nosediving towards the ground. The aircraft was destroyed, and the pilot who was the sole occupant was fatally injured.

Figure 1: Accident location with reference to Coober Pedy and the Stuart Highway

Figure 1: Accident location with reference to Coober Pedy and the Stuart Highway

Source: Google Earth, annotated by the ATSB

Context

Pilot information

The pilot, a New Zealand citizen, held a Civil Aviation Safety Authority Part 61 Commercial Pilot Licence (Aeroplane) with a single and multi-engine class rating with endorsements for retractable undercarriage, manual propeller pitch control, and low-level and instrument ratings. The pilot’s commercial licence was issued on 17 August 2023 in accordance with the Trans-Tasman Mutual Recognition Act 1997. The pilot held a Class 1 Aviation Medical Certificate with no restrictions, valid to 29 November 2024. 

At the pilot’s last medical examination on 6 November 2023, the pilot reported having 251 hours of total aeronautical experience.

Aircraft information

VH-SQO was a Cessna Aircraft Company 172N 4-seat, single-engine, high (strut-braced) wing, all metal, unpressurised, fixed (tricycle) undercarriage aircraft. The aircraft was manufactured in the United States in 1978 and first registered in Australia on 29 August 1978. The operator had been the registered owner of the aircraft since the date of registry. 

The current maintenance release was issued on 8 March 2024 and was valid until 8 March 2025 or 14,620.8 hours total time-in-service, whichever came first. At the time of take-off for the accident flight, the aircraft had accumulated 14,602.7 hours.

Meteorological information

Witnesses reported that on the morning of the accident, the weather was fine, clear and the temperature was cool, not cold. No wind or cloud cover was observed, and the conditions were described by a witness as being ‘almost perfect for paddock work’. 

Wreckage examination

The ATSB’s onsite examination found that the aircraft impacted with terrain at about a 70° pitch down attitude, with ground impact marks directly under the nose showing no forward momentum (Figure 2). The aircraft’s flight controls and structure did not identify any pre‑existing faults or pre‑impact defects or failures. Additionally, one of the propeller blades showed significant rotational abrasion damage and chord-wise twisting indicating that the engine was driving the propeller under significant power at the time of impact. 

Figure 2: VH-SQO accident site

Figure 2: VH-SQO accident site

Source: ATSB

Further investigation

To date, the ATSB has examined the aircraft wreckage, interviewed witnesses, and gathered electronic devices from the accident site. The investigation is continuing and will include consideration of the following:

  • evaluation of witness information
  • examination of the:
    • GPS device recovered from site
    • aircraft maintenance history
    • aircraft weight and balance, and performance
  • meteorological conditions
  • impact sequence and survivability
  • the conduct of similar flight operations
  • pilot qualifications, experience and medical information
  • regulatory requirements for fixed-wing aerial mustering.

A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2024 

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.

The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. 

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2024-037
Occurrence date 27/06/2024
Occurrence time and timezone 09:10 Australian Central Standard Time
Location Near Mulgathing Station
State South Australia
Report release date 01/05/2025
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Cessna Aircraft Company
Model 172N
Registration VH-SQO
Serial number 17270255
Aircraft operator Mulgathing Proprietary Limited
Sector Piston
Operation type Private
Activity General aviation / Recreational-Aerial work-Agricultural mustering
Departure point Mulgathing Station, South Australia
Destination Mulgathing Station, South Australia
Injuries Crew - 1 (fatal)
Damage Destroyed