On 19 August 2013 the container ship Mell Selarang berthed at number three berth in the Port of Townsville, Queensland. Stevedores started cargo operations.
Cargo operations continued into 20 August and, at about 0752, the stevedores stopped work for a change of shift. In the quiet period between the two shifts, one of the ship’s seamen decided to grease the hatch landing pads around the open cargo hold when he slipped and fell, landing about 8.5 m below on the top of a container in the cargo hold.
Safety message
This incident highlights the fact that seemingly simple tasks that are undertaken with the best of intentions often have the planning and risk assessment stages inadvertently overlooked. This is particularly the case when the task is undertaken when an unexpected and opportune moment arises to complete the task.
The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. One of the current safety concerns is marine work practices.
On 26 August 2013, a flight instructor and student pilot were conducting night circuits in a Cessna 172 aircraft, registered VH‑RQZ (RQZ), at Archerfield Airport, Queensland. There were also two other aircraft conducting circuits. The student pilot of RQZ broadcast a call on the CTAF downwind leg of the circuit for runway 10. The pilot of an Agusta AW139 helicopter, registered VH-ESZ (ESZ), then broadcast an inbound call advising they were 5 NM to the north at 1,400 ft above mean sea level.
The pilot of ESZ reported sighting two other aircraft in the circuit and noted that they were unlikely to come into conflict with ESZ.
The student pilot of RQZ then broadcast a call turning base for a touch-and‑go on runway 10 and stated that they were conducting a simulated landing light failure.
About 15 seconds later, the pilot of an instrument flight rules (IFR) aircraft asked the pilot of RQZ to confirm his position, to which the instructor replied that they were turning onto final. Shortly after, the pilot of ESZ broadcast a call advising that he was on a tight left base for runway 10.
When RQZ was on final, the instructor sighted ESZ on a close base in his 10 o’clock position, about 1 NM away and broadcast a call asking the pilot of ESZ whether he had RQZ sighted, but did not hear any response. He then conducted a go-around to ensure separation with ESZ.
When at about 300 ft above ground level, the pilot of ESZ sighted RQZ in his 4 o’clock position, about 100 ft below and 100 m behind ESZ and instructor of RQZ then broadcast that they were going around. The pilot of ESZ tightened the turn onto final and elected to land on the taxiway parallel to runway 10. He had not received a traffic collision avoidance system (TCAS) alert on any aircraft other than the IFR aircraft.
On 14 August 2013, at about 0830 Central Standard Time, the pilot of a Beech BE58 aircraft, registered VH‑ECL, was preparing for a charter flight from Tindal to the Borroloola aeroplane landing area (ALA), Northern Territory.
Using the operator’s elected fuel flow rate for the aircraft of 125 L/hr, the pilot calculated that a minimum of 545 L of fuel was required. The pilot elected to carry 570 L. In preparation for the flight, the pilot referenced the flight data log, which indicated that about 267 L of fuel was on board the aircraft. Consequently, the pilot refuelled the aircraft, adding about 153 L into each of the main fuel tanks. The pilot then conducted fuel drains and found no contaminants present.
During the cruise, the pilot observed the fuel quantity gauge for the right main fuel tank reading zero, but the fuel flow, and engine temperature and pressure indications were normal. The aircraft landed at Borroloola and the passengers disembarked. The pilot re‑checked the fuel calculations and determined that there was sufficient fuel on board for the return trip. The pilot noted that the right fuel quantity gauge was still reading zero and the fuel quantity gauge for the left main tank was indicating about three-quarters full.
On the return flight, when about 50-60 NM from Tindal, the right fuel flow gauge dropped to zero. The pilot shut down the right engine, notified air traffic control and conducted a single-engine landing at Tindal.
This incident highlights the importance of establishing known fuel status regularly and the need to use multiple sources to determine fuel quantity. This is particularly important for determining accurate fuel flow rate calculations and when the fuel quantity on board can only be accurately determined when the fuel tanks are full.
On 26 August 2013, about 2 hours after last light on a dark night, an Alliance Airlines Fokker F28 aircraft, registered VH‑JFB, was taxiing at Williamtown Airport, New South Wales.
As the captain taxied the aircraft onto the runway, air traffic control (ATC) issued departure instructions and a take-off clearance. The captain then momentarily looked down to confirm that the correct departure heading had been entered into the aircraft’s flight management system. As he looked up, he believed he had almost overshot the runway centreline as he observed the threshold markings in front and under the nose of the aircraft, and a line of recessed lights to his left. The captain determined that the recessed lights were runway centreline lights.
Shortly after, the captain commenced the take-off run. Immediately after, the captain noted that the ground area to the left of the runway centreline lights ahead was a different colour than that on the right. He then realised that he had lined up on the runway edge lights. The captain rejected the take-off and steered the aircraft to the right, toward the actual runway centreline.
An internal investigation conducted by Alliance Airlines found that the design of the operational readiness platform (ORP) recessed lighting and obscured centreline markings caused visual confusion during the line-up procedure. This was further compounded by an unserviceable aircraft taxi light and the distraction caused by the requirement for the crew to enter the heading issued by ATC as part of the departure instructions at a critical time. As a result of this occurrence, Alliance Airlines have released an operational notice to crews to increase pilot awareness of ORPs at military airports, and as part of the operator’s accident prevention program, a Take-off Misalignment Hazards publication has been issued.
The Department of Defence also advised the ATSB that scheduled remediation works, which consisted of repainting the runway centreline markings and refreshing the taxiway lead in lines with black contrast lines to highlight the markings had been completed.
In 2010, a research report published by the ATSB identified eight factors common to misaligned take-offs at night, and developed a pilot information card to assist crews in identifying factors that increase the risk of a misaligned take-off.
At 0630 on 8 July 2012, the mess-man on board the Cyprus registered bulk carrier Blue Wave failed to present for duty whilst the ship was off the coast of New South Wales en route to Newcastle. The master was informed, and the crew searched the ship. However, the missing man was not found and so the master advised the Rescue Coordination Centre (RCC) Australia.
In response, RCC Australia tasked air and sea assets to assist the ship in a search of the sea area. The missing man was not located.
Once search operations were discontinued, Blue Wave continued its voyage to Newcastle.
On 9 July 2012, the Cyprus Department of Merchant Shipping requested assistance from the Australian Transport Safety Bureau (ATSB) in obtaining information in relation to the accident.
On 17 July, the information obtained by the ATSB, including statements Police had taken from the crew, was forwarded to the Cyprus Department of Merchant Shipping.
This ATSB external assistance investigation was then closed. Further information in relation to this accident can be obtained from the Cyprus Department of Merchant Shipping.
Pacific National train 9337N left Moss Vale bound for Narrandera, NSW. The train consisted of two locomotives (8113 and 8109) hauling 15 empty wagons for a total length of 295.2 m and weight of 634.6 gross tonnes.
While travelling towards Junee, the train crew’s attention was drawn towards the track works on the Down Main line. Consequently, the crew did not notice the distant Warning sign located at the 482.000 km point, 2000 m prior to the Stop sign. At about 0955, while approaching Junee at a speed of approximately 50 km/h, the train crew observed the Stop sign ahead and immediately placed the brake handle into the emergency position. The train passed over the 3 detonators placed at the Stop sign and came to a stand approximately 75 m past their limit of authority.
The Network Controller (located in Junee) was advised of the incident and the train crew relieved. Both drivers were tested at Cootamundra which proved negative for the presence of alcohol or drugs.
The train crew had been distracted by the track works on the Down Main line between the 479.500 km and 483.500 km points. As a result, they did not see the Warning sign. It is likely that had they noticed the Warning sign they would have taken appropriate action to stop train 9337N at or prior to the Stop sign.
Safety message
The ATSB SafetyWatch initiative highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. One of the safety concerns is safe work on rail.
This occurrence demonstrates the importance of train crews remaining vigilant while carrying out the driving task, especially where a method of special working has been implemented due to track work.
At about 0834 on 10 August 2013, freight train 9101 derailed at a failed mechanical rail joint between Tempy and Bronzewing in Victoria. Nine wagons located mid-consist derailed and separated from the consist with three wagons ending on their side. The two locomotives and the leading 21 wagons and the last 10 wagons remained on the track. Approximately 300 m of track was destroyed as a result of the derailment. There were no injuries to train crew in the incident.
What the ATSB found
The ATSB found that the mechanical rail joint failed due to the development of fatigue cracks in both fishplates resulting in their subsequent overload fracture. The fatigue cracks had originated in the top surface of each fishplate and it is possible that differential sleeper support may have contributed to higher than normal cyclic tensile stress in the fishplates. Lower than required fishbolt torque was also identified and it is possible that movement within the joint may also have contributed to the development of the fatigue cracks, and the subsequent joint failure.
The fatigue cracks had developed over a period of time and the overload fractures had occurred prior to train 9101. Movement of the separated rail ends during the passage of train 9101 resulted in a lateral discontinuity in the running rail at the joint and the train’s derailment.
The ATSB found that the degraded and deteriorating condition of the rail joint was not detected by track inspections. In the 27 months preceding the derailment, visual inspections of this section of track had been conducted solely from rail vehicles and track walking inspections had not been conducted at intervals specified by maintenance procedures.
What's been done as a result
V/Line has updated its maintenance system to generate automated work orders for track walking inspections. In order to improve the detection of track defects, maintenance staff have been provided with specific inspection criteria for track infrastructure including joints and fastenings in their work orders.
Safety message
The implementation of effective inspection and maintenance regimes for the early detection and management of track defects is critical to the safety of rail operations.
On 15 August 2013, a Boeing 777 aircraft, registered VH-VPF and operated by Virgin Australia International Airlines, was conducting a visual approach to runway 34 at Melbourne Airport, Victoria. During the approach and after the waypoint SHEED, the aircraft descended below the approach path to about 500 ft above ground level. Upon recognising the descent profile error, the captain disengaged the autopilot and flew the aircraft level, re-intercepting the profile and continuing the approach to land.
What the ATSB found
The ATSB found that during the construction of the visual approach in the aircraft’s flight management system, the captain inadvertently entered an erroneous height against a waypoint, which was lower than required for that point. This resulted in the aircraft increasing the descent rate to meet this constraint, during which time it descended below profile. While the ATSB was not able to determine what led to the erroneous data entry or the error not being detected, a number of factors were identified that may have influenced the non-detection.
The ATSB also found that, due to extended wakefulness, the crew were probably experiencing fatigue at a level that has been demonstrated to affect performance, although fatigue could not be confirmed as contributing to the error in developing the approach profile. In addition, the ATSB noted that the guidance provided in the operator’s Route and Airport Information Manual increased the potential for the incorrect altitude to be entered into the aircraft’s flight management system for the waypoint.
What's been done as a result
The ATSB has been advised by Virgin Australia International Airlines that the SHEED approach is no longer available for use by its Boeing 777 crews.
Safety message
This occurrence highlights the factors that can influence the accuracy of data entry in critical systems and any associated checks. In addition, it reinforces the importance of monitoring descent profiles, irrespective of any expectation that the descent is being appropriately managed by the autoflight system, and taking appropriate action when a deviation from the desired profile is detected.
The occurrence
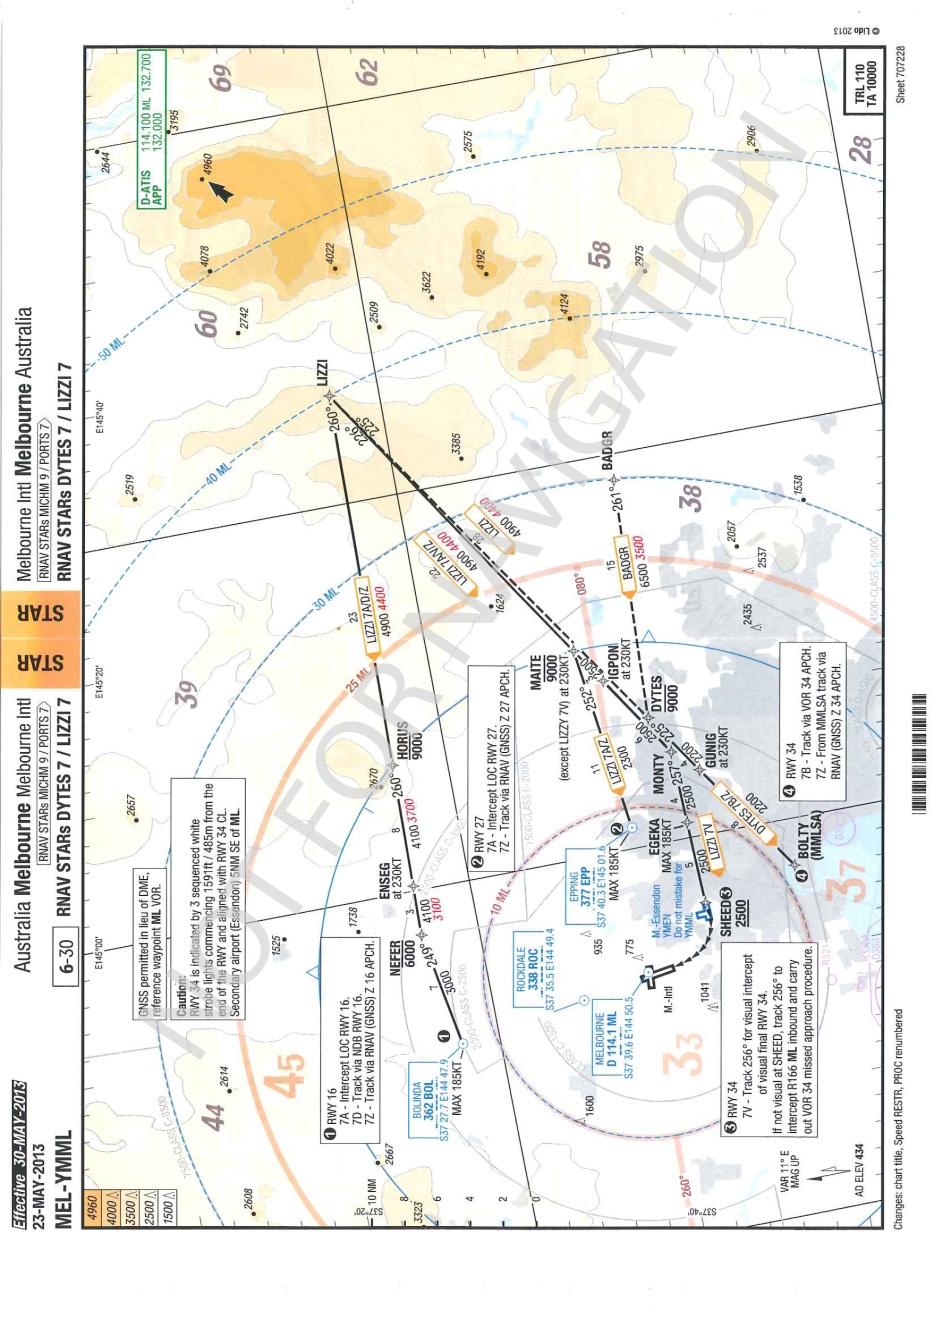
On 15 August 2013, a Boeing 777-3ZGER (B777), registered VH-VPF and operated by Virgin Australia International Airlines (Virgin), was on a scheduled flight from Los Angeles, United States to Melbourne, Victoria with 17 crew[1] and 272 passengers on board. The flight was cleared for an approach and landing on runway 34 at Melbourne Airport via the LIZZI SEVEN VICTOR (LIZZI 7V) standard arrival route (STAR) via the MAITE, IGPON, MONTY, EGEKA and SHEED waypoints (Figure 1). The captain was the pilot flying and the first officer (FO) was the pilot monitoring the approach.
Figure 1: Aeronautical chart for Melbourne LIZZI 7 STAR
Source: Virgin
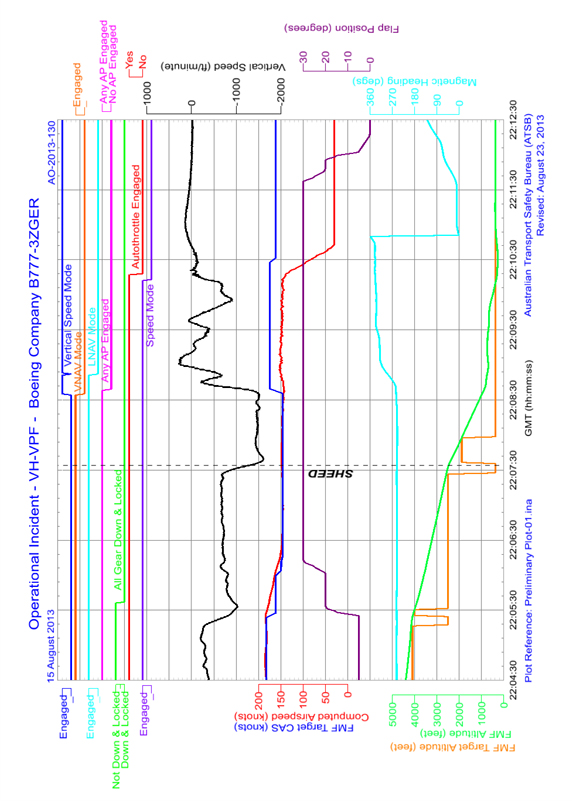
During the STAR, the aircraft was fully configured for the final approach with the landing gear down and landing flaps set. The autopilot was engaged in both vertical and lateral navigation modes.[2] At about 0810 Eastern Standard Time,[3] after passing waypoint SHEED,[4] the final waypoint in the STAR, the autopilot increased the rate of descent from about 700 ft/min to about 1,500 ft/min. This was greater than the crew were expecting and the FO alerted the captain to the high descent rate. As the captain expected it to reduce and stabilise at the anticipated rate, they decided to continue the approach and monitor the aircraft’s rate of descent.
Noting that the captain was concentrating on the information presented on the aircraft’s flight instruments, the FO turned their attention outside of the cockpit to visually monitor the approach to the runway, which they had sighted to the right of the aircraft. The FO noted that the approach appeared to be too low and alerted the captain, who agreed and attempted to reduce the rate of descent by engaging the vertical speed mode of the autopilot flight director system. The captain then disconnected the autopilot and took manual control of the aircraft. The aircraft was levelled off at about 700 ft above mean sea level (AMSL), or about 500 ft above ground level, and turned to the right to align with the runway. The FO alerted the captain to the precision approach path indicator (PAPI)[5], which was showing four red lights, indicating that they were well below the correct glide path.
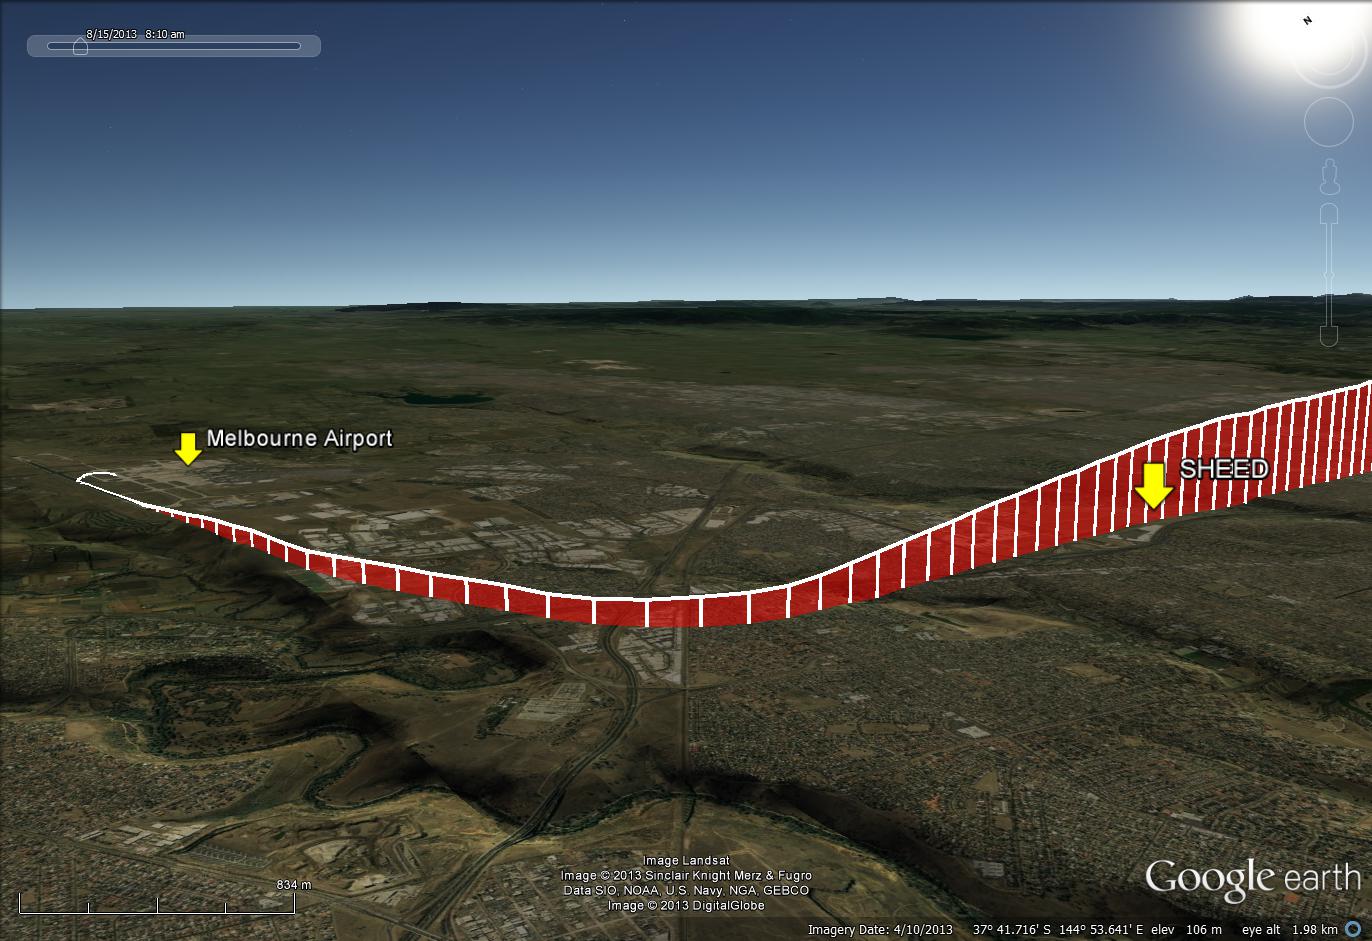
The aircraft was flown level until re-established on the correct glide path for a normal approach and landing. Figure 2 shows the aircraft’s flight path during the approach and landing.
Figure 2: Approach flight path into Melbourne Airport
Source: Google earth, modified by the ATSB
Preparation for the approach
Prior to descent into Melbourne, while the FO was on a rest break in the flight crew rest compartment, the captain decided that, although runway 27 was the active runway for arrivals, they would land on runway 34. The captain reported that this decision was based on the increased landing distance available with runway 34 and on more favourable crosswind conditions for the landing. A number of routes were available for the approach and landing on runway 34, including a visual approach, which the captain elected to conduct via the LIZZI 7V STAR.
In accordance with Virgin standard operating procedures, as the pilot flying, the captain selected the runway 34 waypoint (RW34)[6] from the database in the aircraft’s flight management system (FMS) and the LIZZI 7V STAR from the available approach options for that runway. The LIZZI 7V STAR ended at the SHEED waypoint, which is not aligned with the runway 34 centreline. This meant that connecting the flight plan directly from SHEED to RW34 (representing the runway threshold) would have resulted in a final approach that did not track along the runway centre-line. To account for this and more appropriately align the final approach with the runway centre-line, the captain used a feature in the FMS that produced an additional waypoint (labelled RX34) that was offset back along an extended runway centre-line.
The target altitude for RX34 was automatically calculated by the FMS based upon the position and altitudes of the RW34 and SHEED waypoints. In accordance with the advice in the Virgin Route and Airport Information Manual,[7] the captain entered a runway extension of 2.8 NM (about 5 km) into the FMS, which created RX34 (see the section titled Briefing paper). They also intended to amend the altitude of the RW34 waypoint to 380 ft as per the recommendation in the manual, although the altitude was inadvertently entered into RX34 rather than RW34.
The captain reported that the cruise relief FO, who had replaced the FO during their rest break and was occupying the right seat at the time, checked the information that was entered into the FMS before the flight plan was activated. The captain also reported not specifically requesting the cruise relief FO to validate the data entered into the FMS.[8]
When the FO returned to the flight deck after their rest break, and as part of the before descent checks, they checked and validated the arrival and approach data entered into the FMS. The FO reported some confusion during those checks as a result of noticing that the FMS did not present the expected glide path angle for the final legs of the approach. The FO queried this with the captain, who informed the FO that the FMS did not present that information for a manually constructed approach. The FO accepted this explanation and continued with the before descent checks. The FO recalled reviewing the Route and Airport Information Manual during the checks and checking that the altitude value of 380 ft was correct, but did not identify that the altitude had been entered into RX34 rather than the intended RW34.
The flight crew consisted of a captain, a first officer (FO) and, due to the duration of the flight, two cruise relief FOs. The captain and FO were in the operating seats during the take-off and landing.
The flight was a long-range flight that was rostered as a 17-hour duty, with a 15hour flight time. Given the duration of the flight, Virgin Australia Airlines (Virgin) provided rest periods for the operating crew during the cruise. The role of a cruise relief FO was to replace an operating crew member to allow them to rest as required in the flight crew rest compartment when established in cruise. The flight was operated according to Virgin’s fatigue risk management system, which was approved by the Civil Aviation Safety Authority. A review of the fatigue risk management system found that it met the current best practice guidance available from the International Civil Aviation Organization.
Captain
The captain held an Air Transport Pilot (Aeroplane) Licence (ATPL(A)) and was endorsed to operate B777 aircraft. They held a valid Class 1 Aviation Medical Certificate with a restriction that reading correction was to be available whilst exercising the privileges of the licence.
The captain’s aeronautical experience is outlined in Table 1.
Table 1: Captain's aeronautical experience
Total flying hours
12,500
Total flying hours on the B777
6,423
Total flying hours in the last 90 days
131.9
Total flying hours in the last 30 days
47.6
Total flying hours in the last 7 days
28.8
In addition to their operational flight duties, the captain was also an approved check and training captain. The captain reported having recently completed a visual approach via the SHEED waypoint to runway 34 in the simulator and once during line operations 4–5 months prior.
The captain had 10 days off, followed by a rostered standby day with no duty, prior to operating the outbound flight from Sydney to Los Angeles on 12 August 2013. Prior to commencing duty for the occurrence flight, the captain had about 35 hours free of duty in Los Angeles and reported obtaining about 13 hours sleep during that time. On the occurrence flight, they obtained 3 hours sleep during a rest break, which was described as ‘good quality’. There was an additional rest break taken during the flight, however no further sleep was obtained. The captain reported feeling tired as the aircraft approached Melbourne but considered this ‘normal’ for the length of the flight.
First Officer
The FO held an ATPL(A) and was endorsed to operate B777 aircraft. They held a valid Class 1 Aviation Medical Certificate with nil restrictions.
The FO’s aeronautical experience is outlined in Table 2.
Table 2: FO’s aeronautical experience
Total flying hours
10,176
Total flying hours on the B777
2,658
Total flying hours in the last 90 days
141
Total flying hours in the last 30 days
28
Total flying hours in the last 7 days
28
In addition to their operational flight duties, the FO was also an approved training FO, and was providing training to one of the cruise relief FOs during the flight.
The FO reported that they had flown into Melbourne on four previous occasions, but that this was their first experience of a visual approach to Melbourne Airport runway 34 via the SHEED waypoint. They had previously conducted the approach in the simulator, but reported that they had not done so for over 18 months.
Prior to operating the outbound flight to Los Angeles, the FO had 2 rostered days off and a standby day with no duty. They also had about 35 hours free of duty in Los Angeles and reported obtaining about 16 and a half hours sleep. The FO reported this as ‘good quality’ sleep and that they obtained about an hour’s sleep during the first inflight rest break and about an hour and a half during the second rest break. The FO reported feeling alert at the start of the flight and tired on arrival at Melbourne, which was considered ‘normal’ given the flight time. The FO felt that the provision of training to one of the cruise relief FOs increased the FO’s level of tiredness.
Cruise relief First Officer 1
The first of the cruise relief FOs held an ATPL(A) and was endorsed to operate B777 aircraft. They held a valid Class 1 Aviation Medical Certificate with a restriction that distance vision correction must be worn whilst exercising the privileges of the licence.
The first cruise relief FO’s aeronautical experience is outlined in Table 3.
Table 3: Cruise relief first officer 1’s aeronautical experience
Total flying hours
3,190
Total flying hours on the B777
1,025
Total flying hours in the last 90 days
217
Total flying hours in the last 30 days
86
Total flying hours in the last 7 days
44.5
The first cruise relief FO was occupying the FO’s seat during the FO’s rest period.
Cruise relief First Officer 2
The second cruise relief FO held an ATPL(A) and was endorsed to operate B777 aircraft. They held a valid Class 1 Aviation Medical Certificate with nil restrictions. This cruise relief FO was undergoing line training during the flight.
The second cruise relief FO’s aeronautical experience is outlined in Table 4.
Table 4: Cruise relief first officer 2’s aeronautical experience
Total flying hours
3,641
Total flying hours on the B777
56
Total flying hours in the last 90 days
56
Total flying hours in the last 30 days
56
Total flying hours in the last 7 days
29
Aircraft information
Flight control
The Boeing 777 can be manually controlled by the pilots via a conventional set of flight controls, or automatically using the aircraft‘s autopilot flight director system (AFDS). The AFDS can make a number of control inputs depending on the mode selected. These modes range from holding a selected heading and/or altitude to complete control through a pre-programmed flight management system (FMS) flight path in lateral flight path (LNAV) and vertical flight path (VNAV) modes. The AFDS is controlled through the AFDS mode control panel, located on the instrument panel glare shield in front of the pilots.
Altitude, heading, vertical speed, flight path angle and/or airspeed can all be set by the flight crew through the mode control panel and either automatically controlled by the autopilot or displayed to the flight crew on the flight director on the flight displays. Alternatively, guidance information for a pre-determined flight path can provided to the AFDS through the FMS.
Flight management system
The FMS is an integrated electronic system that provides the flight crew with various functions including navigation, performance optimisation and fuel monitoring, and cockpit displays. The FMS contains functions that manage the aircraft’s lateral and vertical navigation. The FMS incorporates a navigation database that contains the necessary pre-programmed waypoints to fly routes, standard instrument departures (SID), standard arrival routes (STAR) and other standard flight procedures.
A flight plan of the lateral, vertical and speed profiles for a flight can be either uploaded into the FMS as a complete plan or manually constructed by the flight crew using the waypoints contained in the navigation database in the FMS. The FMS then uses the aircraft’s current position and supporting system data to calculate commands for flight path control, which are sent to the AFDS. Map and route data are sent by the FMS to the navigation displays for visual presentation to the flight crew.
The commands for flight path control are presented to the flight crew through the flight director, which provides command bars on the primary flight display. The flight crew can make manual inputs to the aircraft’s flight controls to attain the flight director commands, or they can be automatically accomplished by engaging the autopilot.
The flight crew’s primary interface with the FMS is via the control display units (CDUs). Three CDUs are located in the centre pedestal, one each for the captain and FO (Figure 3), and a third at the rear of the pedestal, as a backup. Each CDU contains a screen for presenting FMS information and a keypad to allow the flight crew to navigate through the various pages and enter and modify FMS data. The screen contains a number of lines of information with line selection keys that allow each line to be selected to either enter or modify the data in that line. Data is entered into the CDU via the scratchpad, using the keypad at the bottom of the screen. The scratchpad is also used to present messages to the flight crew in relation to the operation of the FMS (Figure 4).
Figure 3: Captain and FO CDUs
Source: ATSB
Figure 4: CDU detail
Source: ATSB
Meteorological information
Observations from the Melbourne Airport automatic weather station were recorded every half hour. The surface weather conditions recorded at 0800 were a temperature of 9 °C, wind direction of 350° at 8 kt, QNH[9] 1019 hPa, with Few[10] cloud at 3,600 ft and visibility greater than 10 km with only a negligible change observed by 0830.
As sunrise was at 0705, and given the observed weather, the approach and landing occurred during daytime visual conditions.
Aids to navigation
Melbourne Airport runway 34 had three approaches available, an RNAV GNSS[11], a VOR[12] and a visual approach. Only the visual approach could be conducted using the LIZZI 7V STAR, as the other two approaches required the use of a different STAR that routed the aircraft over the BOLTY waypoint. BOLTY was further to the south of Melbourne Airport, before turning onto the final approach heading.
The LIZZI 7V STAR commenced at the LIZZI waypoint north-east of Melbourne Airport, and sequenced through the waypoints MAITE, IGPON, MONTY and EGEKA before completing at SHEED (Figure 1). SHEED was located overhead Essendon Airport, to the southeast of Melbourne Airport, and had a minimum altitude requirement of 2,500 ft to prevent conflict with traffic around Essendon Airport. All of these waypoints were stored in the database in the FMS.
The flight crew were using maps and charts that were provided by Virgin. The ATSB determined that the chart for the LIZZI 7V STAR/visual approach was valid for the time of the occurrence. The chart showed that the visual segment consisted of a right turn to align with runway 34. The elevation of the runway threshold was 330 ft.
Approach aids
Visual guidance to runway 34 was provided by sequenced lead-in strobe lights to assist crews conduct a visual turn onto final and a precision approach path indicator (PAPI) system, which provided glide path guidance. The PAPI consists of four indicator lights adjacent to the runway that can be either red (indicating low on approach) or white (indicating high on approach) and provides visual vertical guidance to the flight crew to assist them on attaining the appropriate glide path angle.
Melbourne Airport runway 34 has a PAPI on the left and right sides of the runway that are set to provide a glide path angle of 3°. The flight crew reported that the PAPI was not visible until they were on the right turn to align with the runway, which is when they would normally start using it for glide path reference.
Recorded data
The ATSB obtained a copy of the data recorded on the aircraft’s quick access recorder (QAR), including of the occurrence flight. Selected parameters from that data are provided in Figure 5.
Figure 5: Selected QAR data showing the occurrence after passing SHEED
Tests and research
In November 2013, the ATSB participated in a session in Virgin’s B777 full flight simulator to observe the differences in a Melbourne Airport runway 34 visual approach via the LIZZI 7V STAR with the correct and incorrect data entered into the FMS. The following observations were made:
Approach with the correct data in the FMS
During the approach with the correct data in the FMS it was found that after passing SHEED, the rate of descent increased to 1,450 ft/min before it decreased, settling at about 850 ft/min.
Approach with incorrect data in the FMS
During an approach using the data entered by the crew in this occurrence, it was found that:
after passing SHEED, the rate of descent increased to about 1,900 ft/min, before settling to about 1,850 ft/min[13]
the PAPI was not distinguishable until around 1,000 ft and about to commence the turn onto final. At that point, the PAPI was displaying 4 red lights.[14]
Organisational and management information
Operational information
Virgin provided the following information regarding the Melbourne Airport runway 34 visual approach from the LIZZI 7V STAR in their Route and Airport Information Manual (Figure 6).
Figure 6: Presentation of information regarding the visual approach via SHEED in the operator’s Route and Information Manual
An approach and landing on Melbourne Airport runway 34 using a visual approach via SHEED was included as part of Virgin’s refresher training program. In this respect the Instructor Guide for simulator refresher training included the runway visual approach via SHEED as part of a two session refresher training package that included numerous other items of training. The training was structured such that an FO under training would be the pilot flying the visual approach.
The Instructor Guide provided the same information as that contained in the Route and Airport Information Manual, but because the formatting differed from that manual the line break at the end of the second point occurred at a different point within the text and all information about the runway extension was contained on the one line (Figure 7).
Figure 7: Presentation of information regarding the visual approach via SHEED in the operator’s Instructor Guide for refresher training
On 28 July 2013, Virgin’s Flight Training/Standards branch released a Briefing Paper regarding the visual approach via SHEED.[15] The Briefing Paper was released when an analysis by Virgin of a number of occurrences of high rates of descent during the approach were found to result from (in part):
Delayed descent from SHEED
Autopilot disconnect during the turn onto final
FMC programming resulting in an above path PAPI indication when established on final.
A number of recommendations were included in the Briefing Paper in an attempt to prevent recurrence, although none of these had been included in operational procedures at the time of the occurrence. Those recommendations included:
Crew who are tired or fatigued should plan for and require the RNAV GNSS Approach
Briefing for the approach should cover AP [autopilot] use, the likelihood of increased decent rates and the requirement for a delayed stabilisation (500 ft Above Aerodrome Level), including the associated calls
The FMC should be programmed in accordance with the C1 [Route and Airport Information Manual] with a hard altitude at the 2.8nm extension that places the aircraft on a 3° approach (1,270 ft) rather than leaving the higher FMC calculated value
With the FMC programmed, the AP in LNAV/VNAV is available for the approach through the turn to final down to 200 ft AGL. While closely monitoring for acceptable performance – AP use is recommended for the approach.
Vertical path corrections with modes other than VNAV is not recommended – any unacceptable behaviour of LNAV/VNAV must be corrected manually with the AP disconnected of [or] a go-around commenced.
The Briefing Paper also included expanded FMC configuration information (Figure 8).
On 10 January 2013, the crew of an Embraer Regional Jet 170 was conducting a scheduled passenger service from Darwin to McArthur River Mine, Northern Territory. Shortly after passing navigational waypoint SNOOD, 125 NM (232 km) north-west of McArthur River Mine, the aircraft’s flight path started diverging from its planned track. The problem was identified by air traffic control and the crew were advised.
The ATSB found that, while updating the aircraft’s flight management system for the descent into McArthur River Mine, the crew unintentionally omitted entering an intended navigational waypoint that was located 25 NM (46 km) north-west of McArthur River Mine. This omission resulted in the aircraft’s autopilot tracking the aircraft direct to the initial approach fix instead of first tracking to the intended waypoint. The crew’s crosschecking processes were not effective in identifying the data input error.
Data input errors when programming a flight management system (FMS) are not uncommon (PARC/CAST Flight Deck Automation Working Group 2013). They are usually detected by the flight crew before there is any effect on the aircraft’s flight path or performance. On rare occasions, programming errors can lead to problems with the aircraft’s flight path or performance,[18] and on very rare occasions contribute to aircraft accidents.[19]
Although data-entry error has the potential to become a hazard to flight safety, the risk associated with the high descent rate on the occurrence flight was minimal given the approach was in visual conditions and the crew were not experiencing any significant workload or other difficulties.
This analysis examines the various human performance factors identified during the investigation as having influenced the flight crew’s actions and ability to detect the erroneous data.
Data input error and error detection
During the entry of the visual approach into the FMS, the captain inadvertently entered the runway threshold crossing altitude of runway threshold elevation + 50 ft into runway extension waypoint RX34, instead of into the intended RW34. RW34 corresponded with the runway threshold. This resulted in the aircraft descending after SHEED to meet this erroneous waypoint altitude constraint, which was 2.8 NM or about 5 km from the runway threshold and therefore necessitated a higher than normal descent rate to achieve the RX34 altitude constraint as set.
The erroneous entry of the runway threshold crossing altitude at the RX34 waypoint was almost certainly a skill-based error known as a ‘slip’, which is an error in the execution of an action (Reason 1990). Skill-based actions are those which have become so rehearsed and automatic that the individual does not need to closely monitor each stage of the action sequence in the way that they would if the task was less familiar or unknown. Due to this reduced monitoring, the individual will generally not realise that they have carried out an incorrect action until it is either too late to change, or there has already been an unforeseen consequence.
An observational study of airline operations examining error detection and recovery noted that ‘less than half the errors committed by crew were actually detected’ (Thomas, Petrilli and Dawson 2004). A number of factors may have increased the likelihood of the crew not detecting the error on this occasion.
The captain reported that the cruise relief first officer (FO) conducted a crosscheck of the FMS data, but did not ‘validate’ the data against the approach chart or Route and Airport Information Manual. This check was intended to be a gross error check only, and the operational FO was expected to check and validate the data upon their return from a break in the flight crew rest compartment. However, the operational flight crew’s checks may have been degraded because they unintentionally and unconsciously felt that this crosscheck would have detected any error in the data. Although not intended as a formal validation of the data input by the captain, this gross error check by the cruise relief FO was an opportunity for the error to have been identified.
The operational FO had just returned from a rest break and was not expecting to conduct a visual approach. The FO initially questioned the decision to conduct a visual approach, primarily because it required a level of precision which added complexity at the end of a 15-hour flight. However, the captain explained that they had conducted this approach in the simulator and had flown one during line operations. Together with the FO’s perception of the captain’s experience and reputation, this made the FO comfortable enough to accept the captain’s decision to conduct a visual approach.
On review of the FMS, the operational FO identified that, contrary to their expectation, the glide path angle was not displayed. The FO queried this with the captain. While this issue was quickly resolved, it is possible that exploring this issue distracted the FO from the check. The FO recalled checking the Route and Airport Information Manual and that the runway threshold crossing altitude was in the FMS. Regardless, the erroneous position of that altitude was not detected. Although the ATSB was not able to precisely determine what led to the erroneous data entry not being detected, a number of factors were identified that may have influenced the non-detection.
The operator’s Route and Airport Information Manual contained guidance on conducting a visual approach to runway 34 via the SHEED waypoint. The presentation of this information as a sentence that was broken over a number of lines was such that it was possible to associate the words ‘and altitude 0380’ with the runway extension waypoint (RX34), rather than the intended runway threshold waypoint (RW34). This increased the potential for this incorrect altitude to be entered against RX34, rather than the ‘“hard” altitude’ of 1,270 ft as recommended in the Virgin briefing paper.
The possible association of the altitude of 380 ft with RX34 was not the intention of the guidance, nor the deliberate action of the flight crew on this occasion. However, the ATSB noted that if the crew had been able to directly compare the altitudes in the FMS with the associated waypoint in a more graphical presentation, such as the table presented in the Briefing Paper and the accompanying expanded flight management computer configuration information (Figure 8), the probability of detecting the error would have been increased. This would have resulted from the crew’s improved awareness of the three altitudes to check (SHEED, RX34 and RW34), and their ability to individually check each against the appropriate waypoint.
Previous data entry error occurrences have highlighted the role of expectancy in influencing flight crew error detection. On this occasion, the similarity of the waypoint names RW34 and RX34 increased the likelihood that the crew could misinterpret one waypoint for the other when entering and/or checking the data.
The high descent rate after the aircraft passed the SHEED waypoint was initially identified by the operational FO. The captain believed that this was a normal aircraft response (as confirmed by the ATSB in the operator’s simulator) and that the descent would stabilise at a lower rate. When it did not stabilise as expected, the captain’s attention became focused on monitoring the rate of descent on the aircraft’s instruments instead of including in their scan the external flight path cues necessary for conducting a visual approach. Noting the captain’s change of focus, the FO changed attention from monitoring the approach on the aircraft instruments to monitoring the external visual cues. This led to a delayed recognition of, and reaction to, the aircraft’s descent below the intended approach path. It was not until the FO alerted the captain to the approach appearing to be too low, that the result of the descent rate was identified, and action taken by the captain to regain the correct approach profile.
Crew fatigue
The International Civil Aviation Organization (ICAO 2011) defined fatigue as:
A physiological state of reduced mental or physical performance capability resulting from sleep loss or extended wakefulness, circadian phase, or workload (mental and/or physical activity) that can impair a crew member’s alertness and ability to safely operate an aircraft or perform safety related duties.
Fatigue can have a range of adverse influences on human performance. These include slowed reaction time, decreased work efficiency, reduced motivational drive and increased variability in work performance, lapses or errors of omission (Battelle Memorial Institute 1998).
While research indicates that less than 6 hours sleep in the previous 24 hours can increase risk (Thomas and Ferguson 2010), the captain had about 10 hours sleep in the 24 hours prior to departure and the operational FO had about 12 and a half hours. In addition, the flight crew reported obtaining adequate ‘good quality’ sleep during the layover in Los Angeles and feeling well rested at the commencement of the flight. However, the effect of extended wakefulness for both crew and workload due to training duties for the FO meant that both crew were probably experiencing a level of fatigue known to have a detrimental effect on performance.
A fatigue risk management system (FRMS) is designed to manage the fatigue risk associated with operations, including long-haul flights. However, it is not designed eliminate fatigue, such as that experienced by the flight crew. Rather, the FRMS sits within a broader safety management system, which seeks to mitigate the effects of fatigue on performance. In this instance, selection of an instrument approach would have been an example of a mitigation to the fatigue of the crew, rather than conducting the visual approach via SHEED.
The types of errors made by the crew, the slip and then the non-detection of the incorrect waypoint RX34 altitude constraint, are broadly consistent with the effects of fatigue. However as discussed above, there are other possible influences on the development and non-detection of the error and, as such, it is difficult to conclude that fatigue actually contributed to the error and lack of detection on this occasion.
From the evidence available, the following findings are made with respect to the descent below the approach path involving the Boeing 777-3ZGER VH-VPF near Melbourne Airport, Victoria on 15 August 2013. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
When programming the approach into the flight management computer, the captain inadvertently entered the runway threshold crossing altitude into the runway extension waypoint, resulting in the flight management system calculating a vertical flight path that was below the intended approach path and a consequential high descent rate after passing the SHEED waypoint.
When checking the flight management system, the first officer did not detect that the runway threshold crossing altitude had been entered into the runway extension waypoint, missing the opportunity to prevent the unintended approach path and resulting high descent rate after passing the SHEED waypoint.
After passing the SHEED waypoint, the captain's attention became focused on the high rate of descent instead of monitoring external flight path cues as part of the visual approach, causing the first officer to shift their attention to the external cues and leading to a delayed recognition and response to the aircraft's position below the intended approach path.
Other factors that increased risk
The flight crew were probably experiencing a level of fatigue known to have a demonstrated effect on performance.
The presentation of the runway 34 visual approach procedure in the operator's Route and Airport Information Manual increased the potential for the runway threshold crossing altitude to be entered into the runway extension waypoint. [Safety issue]
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Guidance material
The presentation of the runway 34 visual approach in the operator's Route and Airport Information Manual increased the risk of the runway threshold crossing altitude being entered into the runway extension waypoint.
The sources of information during the investigation included:
Virgin Australia International Airlines (Virgin)
the primary flight crew
the Bureau of Meteorology
the Civil Aviation Safety Authority (CASA).
References
Battelle Memorial Institute 1998, An Overview of the scientific literature concerning fatigue, sleep, and the circadian cycle, Report prepared for the Office of the Chief Scientific and Technical Advisor for Human Factors, US Federal Aviation Administration.
International Civil Aviation Organization 2011, Fatigue risk management systems (FRMS): Implementation guide for operators, 1st edition.
Performance-based operations Aviation Rulemaking Committee/Commercial Aviation Safety Team Flight Deck Automation Working Group 2013, Operational use of flight path management systems. Available from www.faa.gov.
Reason, J 1990, Human Error, Cambridge University Press, Cambridge, United Kingdom.
Thomas, MJW & Ferguson, SA 2010, ‘Prior sleep, prior wake, and crew performance during normal flight operations’, Aviation, Space, and Environmental Medicine, vol. 81, pp. 665–670.
Thomas, MJW, Petrilli, RM & Dawson, D 2004, ‘An exploratory study of error detection processes during normal line operations’, Proceedings of the 26th conference of the European Association for Aviation Psychology, Lisbon, Portugal.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the primary flight crew, Virgin, Boeing and CASA.
Submissions were received from the primary flight crew, Boeing and Virgin. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 15 August 2013, at about 1130 Eastern Standard Time, the pilot of a Bell 47G helicopter, registered VH-RTO, was returning to Essendon, Victoria. The pilot was instructed by air traffic control (ATC) to conduct one orbit due to traffic in the area. After completing the orbit, ATC further instructed the pilot to conduct a second orbit.
While maintaining 1,400 ft above mean sea level (AMSL), the second orbit was commenced. Shortly after, the helicopter began to vibrate severely, yaw from side to side in an oscillating motion, and the rotor revolutions per minute (RRPM) decreased. In response, the pilot lowered the collective in attempt to increase the RRPM, rolled on throttle, and manipulated the anti-torque pedals to counteract the yaw. However, the intensity of the vibrations increased, and the oscillating yaw continued.
The pilot continued to manipulate the controls; however, as the helicopter was unable to maintain altitude and RRPM, he elected to conduct an autorotation. The pilot observed a park to his left and broadcast a ‘MAYDAY’ call.
With some power remaining, the helicopter landed in the park with nil injuries or damage sustained.
An engineering inspection identified that a spring in the distributor block of the left magneto was missing, which resulted in cross firing in the distributor and an associated loss of power.
A partial engine power loss presents a more complex situation to the pilot than a complete power loss. This incident highlights the importance of making timely decisions when a situation develops and the benefits of landing as soon as possible, before the situation deteriorates further.
On 2 August 2013, at 1400 Eastern Standard Time, the student of a Cessna 172R aircraft, registered VH‑IMS (IMS), conducted a solo navigation flight from Archerfield to Sunshine Coast via Caboolture, Queensland. After landing at Sunshine Coast Airport, the student taxied the aircraft to the general aviation apron.
Other aircraft were operating in the area and the pilot wanted to ensure he remained clear of them. The pilot noted a fence and power pole on his left, and then focused on an aircraft taxiing in front of IMS. While the pilot was watching the other aircraft taxiing, he advised that IMS may have rolled forward unnoticed. When the pilot commenced a right turn, the aircraft was past the end of the fence and as he turned the aircraft, the left wing collided with a power pole.
The pilot reported that he had learnt a valuable lesson from the accident, in that the flight is not over until the aircraft has been shut down and secured. This incident also highlights the need to keep a good look out during taxi as well as in flight.