At 1446 Eastern Standard Time (EST) on 12 July 2016, a Westwing Aviation Cessna 208 aircraft, registered VH-NTQ (NTQ), departed Horn Island Airport, Queensland (Qld), for a scheduled passenger flight to Cairns, Qld, with a pilot and seven passengers on board.
As the aircraft climbed towards the planned cruising altitude of 9,000 ft, the pilot began to feel light-headed, dizzy and short of breath. The pilot levelled the aircraft at 9,000 ft and engaged the autopilot. They then attempted to identify a reason for the symptoms, selected air conditioning off, opened a fresh air vent and ate a snack. No reason for the symptoms could be identified. As the flight continued, the symptoms intensified, the pilot felt tingling in their hands and fingers, and large head movements caused severe nausea.
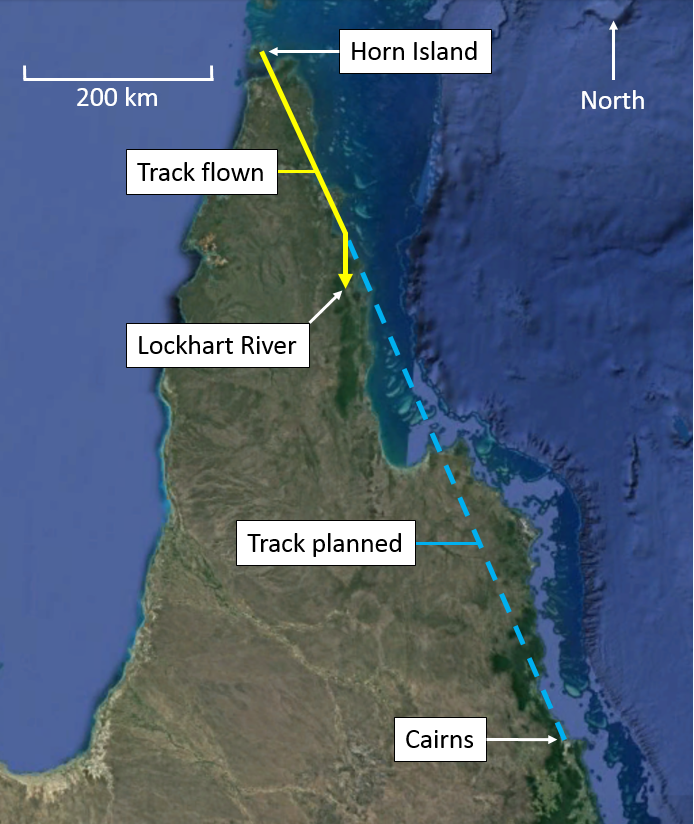
About 20 NM north of Lockhart River, the aircraft approached a significant over-water segment. The pilot assessed that the symptoms would not pass and elected to divert to Lockhart River (Figure 1).
The aircraft landed at Lockhart River without further incident, the pilot and passengers were not injured, and the aircraft was not damaged.
Figure 1: Overview of planned flight
Source: Google Earth, modified by ATSB
Pilot comments
The pilot of NTQ provided the following comments:
They were well rested and fit to fly prior to commencing the day’s duties.
Prior to departing Horn Island, they were well nourished and hydrated.
While conditions were not perfect, they elected to conduct a visual approach as large head movements exacerbated their symptoms.
They had no pre-existing conditions which may have contributed to the incident.
After landing, the symptoms quickly subsided and have not recurred.
Operator comments
The operator of NTQ provided the following comments:
An engineering inspection of NTQ identified no defects. The aircraft has returned to service with no abnormalities reported.
The operator interviewed the passengers the following day. No passenger reported experiencing symptoms similar to the pilot.
After landing, an inspection of passenger baggage and aircraft cargo identified no dangerous goods.
Medical examinations
The pilot underwent medical examinations after landing in Lockhart River and the following day in Cairns. No contributing irregularities were identified.
ATSB comment
While the pilot did not return to Horn Island at the onset of the symptoms, the pilot’s decision to divert to an en route airport as the symptoms intensified rather than continuing to the intended destination demonstrates appropriate cautiousness in the face of uncertainty about their own ability to continue the flight.
Safety message
The ATSB safety education publication Pilot incapacitation occurrences 2010–2014 (AR-2015-096) documents recent pilot incapacitation occurrences in high-capacity air transport, low-capacity air transport, and general aviation to help educate industry about the causes and risks associated with inflight pilot incapacitation.
The ATSB report Pilot incapacitation: Analysis of medical conditions affecting pilots involved in accidents and incidents examined medical conditions and incapacitation events between 1 January 1975 and 31 March 2006. This report concluded that the majority of pilot incapacitation events do not involve a chronic or pre-existing medical condition. They are largely unforeseeable events, often involving acute illnesses or injury. Many are not in themselves life-threatening, but are capable of impairing a pilot’s performance to the extent that safe operation of the aircraft may be adversely affected.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
At about 1541 on 13 July 2016, a Warrnambool-bound passenger train collided with a semi-trailer at the Phalps Road level crossing in Larpent, Victoria. The level crossing was fitted with Stop signs and the truck entered the crossing in front of the train.
As a result of the collision, the train’s locomotive and all passenger cars derailed. The locomotive driver, train conductor, 18 passengers and the truck driver were injured. There were no fatalities.
What the ATSB found
The ATSB found that when the truck driver stopped to look for trains, his view along the track was restricted due to the acute road-to-rail angle and the limited view through the truck passenger-side window. The driver’s view was less than that required to see the train and the truck driver entered the crossing and into the path of the train unaware of the train’s approach.
The acute road-to-rail angle of the intersection at the Phalps Road level crossing also meant that the required viewing angle from a road vehicle exceeded the requirements of the Australian Standard for crossing design. At the time of the incident, many other public road crossings on the V/Line regional rail network, including 35 on passenger lines, were also non-compliant with the Australian Standard for crossing design due to their acute road-to-rail angle.
In February 2015, the Phalps Road level crossing was approved for upgrade to active protection. However, neither V/Line nor the Colac Otway Shire Council took measures to mitigate the known risks associated with the sighting limitations at the crossing, pending this upgrade.
At many other acute-angle crossing locations on the network, processes used by V/Line did not result in the deployment of available risk controls.
The train was operated within the speed limit and the handling of the train did not contribute to the collision.
What's been done as a result
The Phalps Road level crossing was upgraded to active protection in August 2016.
V/Line has taken several further safety actions. Of the 35 passenger line crossings non-compliant with sighting angles, 24 have been either upgraded to active protection, had train speed restrictions applied, or in one instance, restricted access gates fitted. Safety actions on the remaining 11 crossings were pending. Several other crossings with sighting non-compliance have been prioritised for upgrade. One has been reassessed as compliant with the standard.
In addition, the Victorian Level Crossing Safety Committee has established a Passive Crossing Working Group. The Group’s activities will include work around low cost technologies for active crossing protection, and exploring the option of including ‘limited sighting’ crossings on the VicRoads heavy vehicle network maps.
Safety message
Rail infrastructure and road managers should ensure that risk assessment processes take account of available risk controls for hazards stemming from poor sighting at acute-angle level crossings and actively pursue their implementation.
Road users should be particularly cautious at passively-controlled acute-angle level crossings where their vision to the left may be affected by the road vehicle cabin design.
The occurrence
On 13 July 2016, V/Line train 8753 was the 1321[1] passenger service from Melbourne to Warrnambool. It consisted of an N Class locomotive and four passenger cars and was crewed by a locomotive driver and conductor.
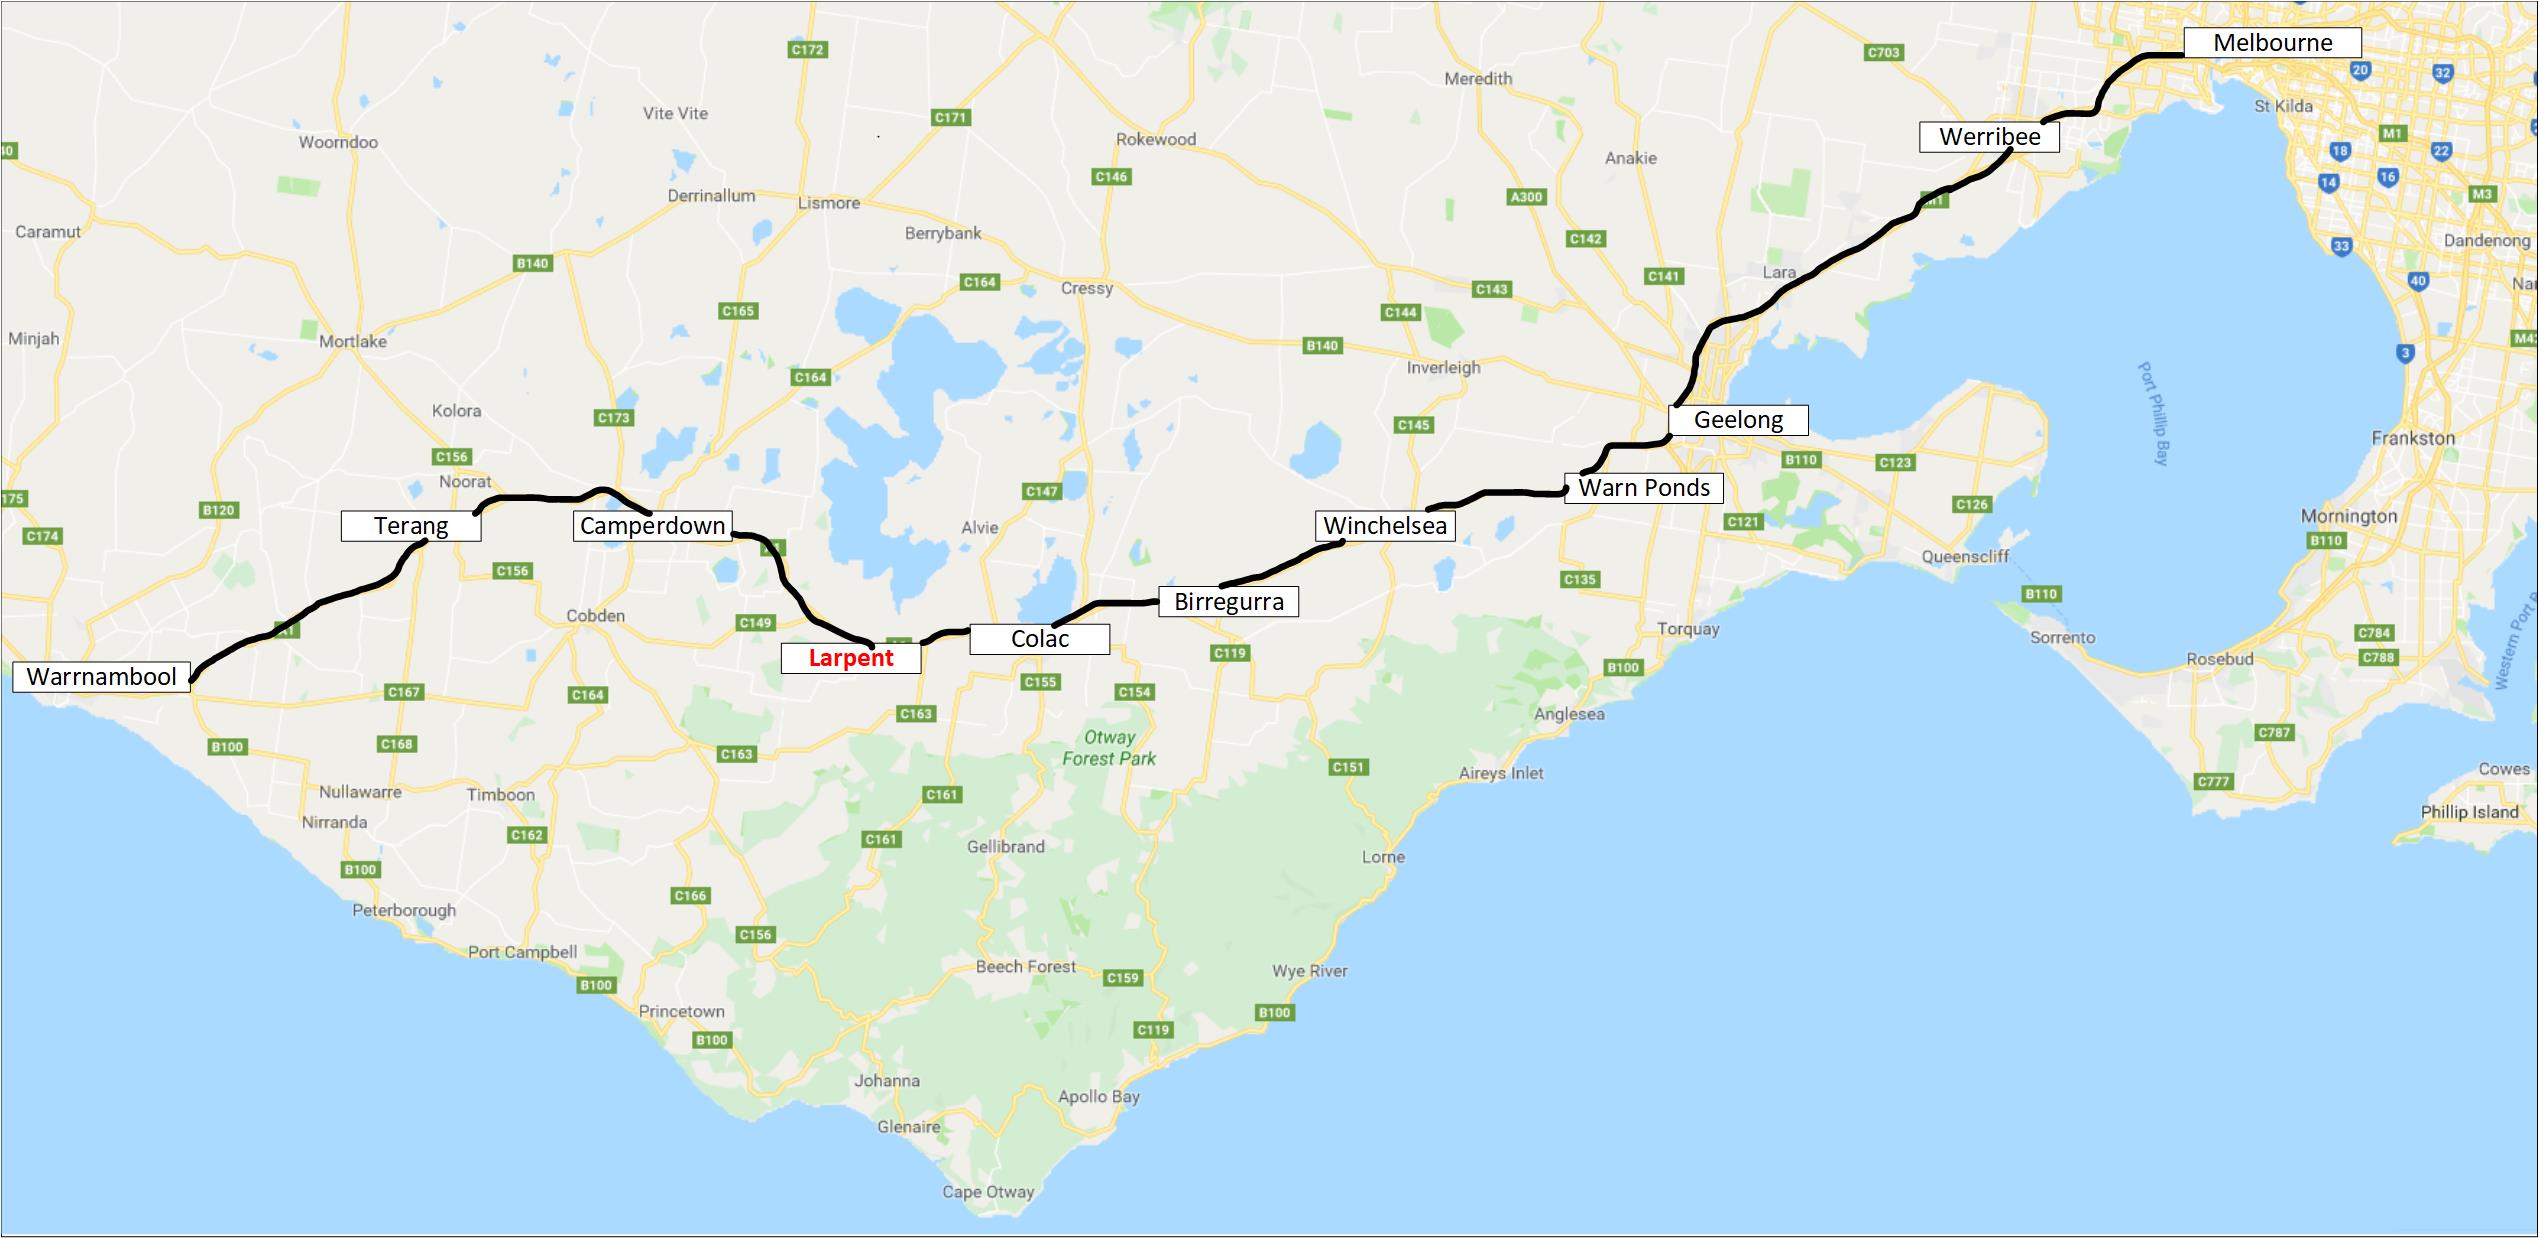
The Phalps Road level crossing was located in Larpent about 85 km west of Geelong. The crossing was 163.886 rail-kilometres from Melbourne on the Broad-Gauge line connecting Melbourne and Warrnambool (Figure 1).
Figure 1: Melbourne to Warrnambool line, and the location of Larpent
The figure depicts the route between Melbourne and Warrnambool. It shows the locations of stations between Geelong on Colac and of the Phalps Road level crossing in Larpent, west of Colac.
Source: Google Earth 2016, annotated by Chief Investigator, Transport Safety (Vic)
The train departed Southern Cross station on schedule. It travelled to Geelong and then to Waurn Ponds where there was a change of driver.
The train departed Waurn Ponds at about 1447. It then stopped at Winchelsea, Birregurra and Colac Railway Stations and departed Colac one minute behind schedule at 1535. Departing Colac, the train was carrying 99 passengers.
On the same day, a truck was to transport stock feed to a farm on Phalp’s Road in Larpent, west of Colac. The truck first travelled to Brooklyn in inner western Melbourne in a stag B Double[2] configuration. In Brooklyn, the truck’s lead trailer was loaded with 26.5 t of bulk stock feed and the rear (stag) trailer remained unloaded.
After departing Brooklyn, the truck travelled to Colac to drop-off the empty rear trailer at the company depot. It then continued towards its destination with the prime mover and lead trailer in a semi-trailer configuration.
Both vehicles were fitted with devices allowing their final approaches to be analysed. The locomotive was fitted with a data logger that recorded train speed and key actions by its driver. The truck location was monitored by a GPS based system.[3]
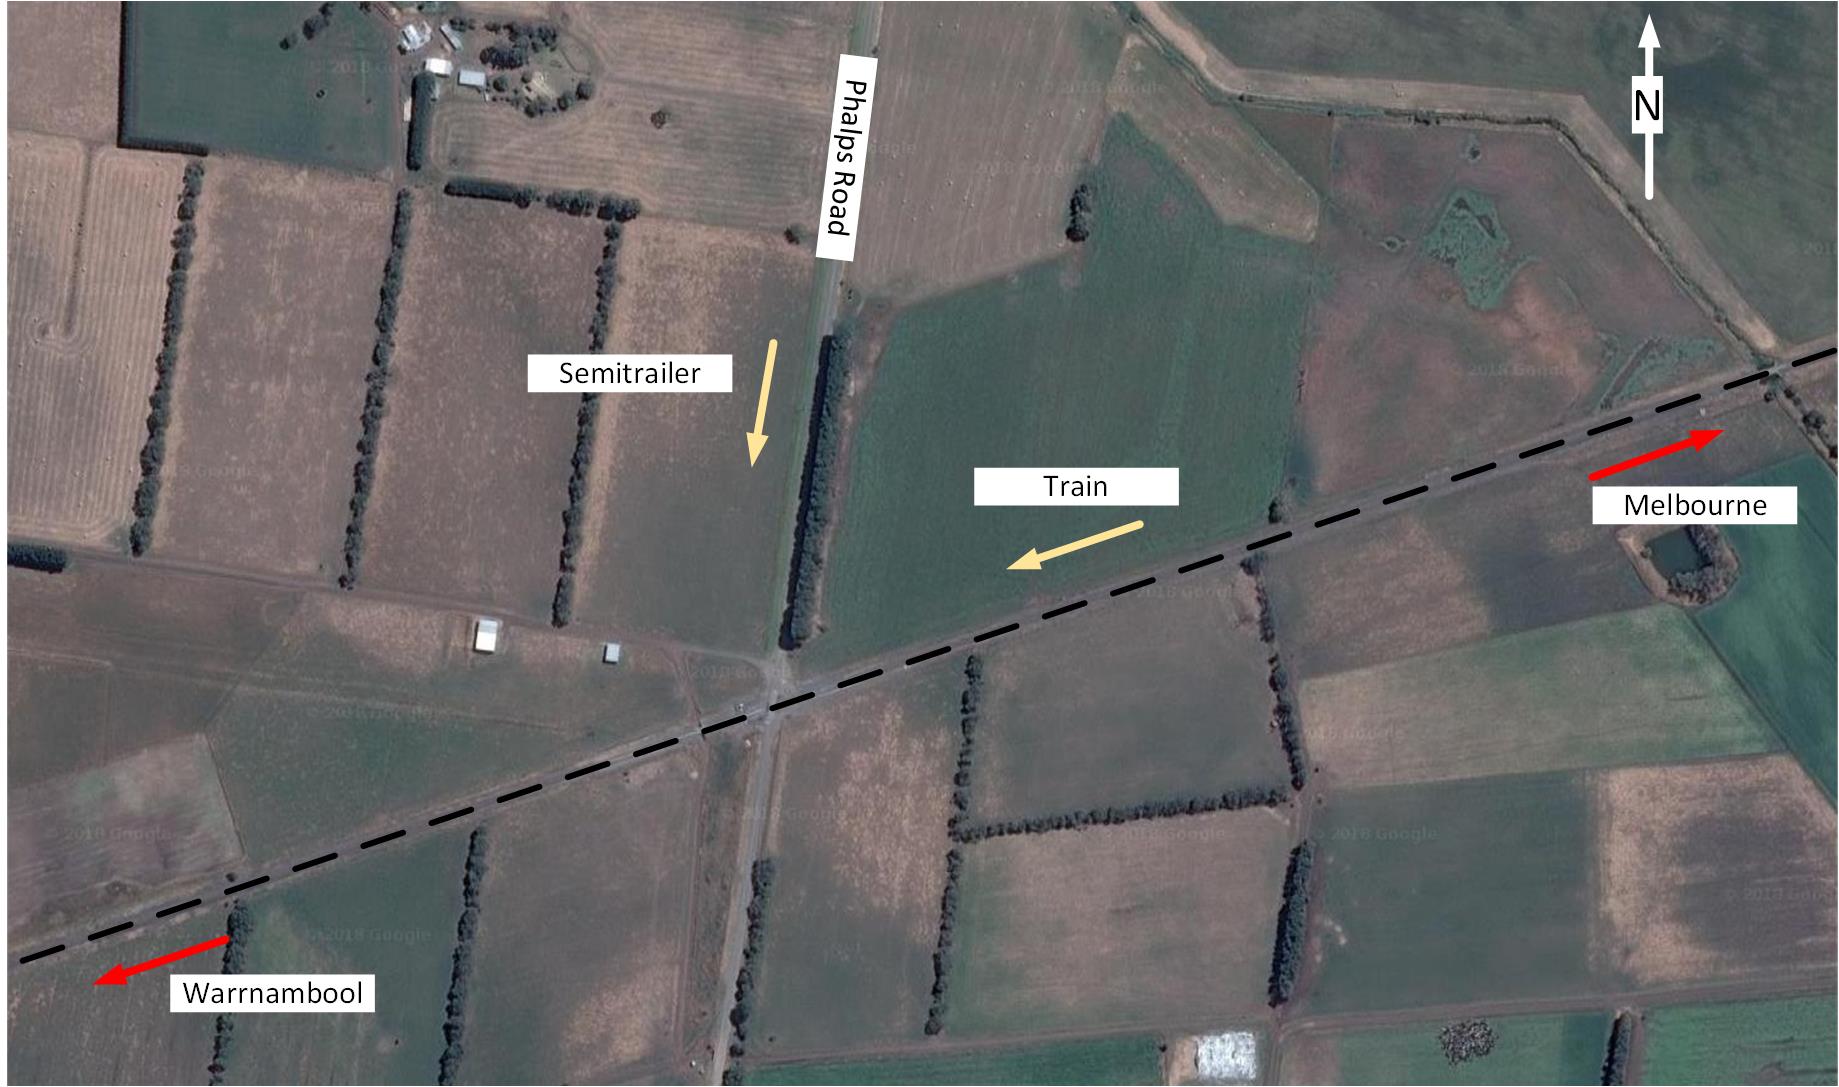
At around 1540, the truck was travelling south along Phalps Road at mostly between 40 and 50 km/h[4] and the train was travelling west (Figure 2).
Figure 2: Overview of truck and train approach to the Phalps Road level crossing
The figure shows an aerial view of the level crossing location, and the direction of each vehicle approaching the crossing.
Source: Image courtesy of MapInfo annotated by Chief Investigator, Transport Safety (Vic)
When the train was about 520 m from the level crossing, the locomotive driver commenced sounding the locomotive’s country horn.[5] At this point the train was travelling at about 109 km/h. The locomotive driver reported observing a truck appear from behind a line of trees along Phalps Road and stop at the level crossing.
The truck stopped 8-to-10 m before the track for about 3 seconds. It then started to move to cross when the train was between 220 and 260 m from the crossing. On observing that the truck had started moving, the locomotive driver again sounded and held the country horn. At this point, the train was about 178 m from the crossing and travelling at about 106 km/h. When the train was about 139 m from the crossing, the locomotive driver made an emergency brake application and braced for collision.
The truck was travelling in first gear and was crossing at around 10 km/h.
When the train arrived at the crossing, the prime mover had cleared the track but its semi-trailer had not. The truck driver heard the train horn shortly before impact and recorded data indicated that the truck speed increased to about 15 km/h in the moment before the collision. The truck driver did not see the train.
At 1541, the locomotive collided with the truck’s semi-trailer at a speed of 95 km/h. The truck was rotated anticlockwise by the collision, and the left side and front corner of the prime mover impacted the side of the train.
The locomotive and all four passenger cars derailed but stayed upright. Both the locomotive driver and the truck driver were seriously injured. The train conductor and 18 passengers sustained minor injuries.
The locomotive sustained significant damage and came to a rest about 120 m beyond the crossing (Figure 3). The collision resulted in severe damage to the prime mover and the semi-trailer (Figure 4).
Figure 3: The damaged locomotive following the collision
The image shows the resting position of the locomotive, its angle of around 45 degrees to the longitudinal direction of the track and the severe impact damage to its leading end. The locomotive and passenger cars remained upright.
Source: Chief Investigator, Transport Safety (Vic)
Figure 4: The damaged prime mover and semi-trailer following the collision
The image shows the severe damage to the prime mover and semi-trailer. The damage to the driving cab was most severe on its left side and the left-front corner.
Source: Chief Investigator, Transport Safety (Vic)
The rail infrastructure was managed by V/Line. The Warrnambool-bound rail approach to the crossing was on tangent track with a true bearing[6] of 253 degrees. The track was on an ascending grade of about 1:63 and the line speed limit was115 km/h. A whistle board was located about 400 m from the crossing.
Drivers of west-bound trains had a direct, straight-ahead view of the level crossing but their view of road traffic on Phalps Road approaching from the north was obstructed by a line of trees along the eastern edge of the road (Figure 5).
Road approach
The road was unsealed gravel and had a posted speed limit of 80 km/h. The level crossing was about 2.3 km south of the Princes Highway and the approach from the north was on a true bearing of about 190 degrees. The line of trees on the eastern edge of Phalps Road extended to within about 50 m of the crossing. The road manager for Phalps Road was the Colac Otway Shire Council.
At the time of the collision, the weather was fine with good visibility. The sun was behind the truck driver and did not affect his observations (Figure 5).
Phalps Road level crossing
Level crossing standard
At the time of the incident, the applicable standard for level crossings was Australian Standard, Manual of uniform traffic control devices, Part 7: Railway crossings (AS 1742.7:2016).[7] The Standard included detailed specifications for level crossing signage and methodologies for evaluating the sighting needs of road users. Compliance with the Standard was not mandated.[8]
Level crossing protection
The movement of road traffic across the Phalps Road level crossing was managed by passive protection[9] that consisted of approach warning signage and Stop signs at the crossing. Road users were required to stop and detect the approach of a train by observation.
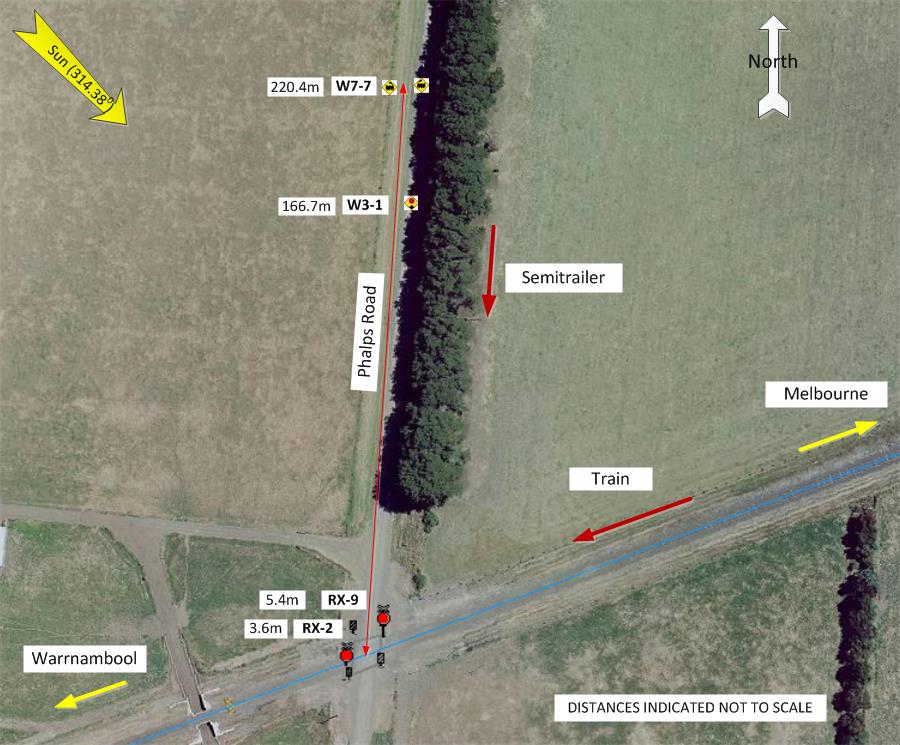
The signage provided on Phalps Road approaching the level crossing was consistent with AS 1742.7:2016. Warning signage on the northern approach included Railway Crossing Ahead (W7-7) signs located 220 m before the crossing and a Stop Sign Ahead (W3-1) sign as the second warning sign (Figures 6 and 7). The W3-1 sign was located about 167 m in advance of the crossing, within the 120-180 m specified in the Australian Standard.
Figure 5: Signage on approach to Phalps Road level crossing from the north
This figure depicts an aerial view of the level crossing and the distances to road signage.
Source: Pass Assets, Public Transport Victoria, annotated by Chief Investigator, Transport Safety (Vic)
Figure 6: Signage on Phalps Road approaching from north.
The image shows the view for a road-user about 250 m from the crossing. The Railway Crossing Ahead signs (W7-7) are in the foreground, and the Stop Sign Ahead sign (W3-1) beyond.
Source: Chief Investigator, Transport Safety (Vic)
Signage at the crossing was in good condition. It included a Railway Crossing Stop Assembly (RX-2) and Railway Crossing Width Marker Assembly (RX-9) located a short distance in advance of the crossing (Figure 7).
Figure 7: Signage at the crossing when approaching from the north
The image is a close-up view of the crossing showing the level crossing signage.
Source: Chief Investigator, Transport Safety (Vic)
Level crossing geometry
Following this incident, an independent[10] survey was made of the Phalps Road level crossing. The results were compared with a previous survey conducted in 2009 as part of the Australian Level Crossing Assessment Model (ALCAM) process (Figure 8).
The table shows the measured bearings of track and road at the Phalps Road level crossing, and the substantial errors of up to 41 degrees in the survey conducted in 2009.
Source: ALCAM data from VicTrack, post-incident survey contracted by the Office of the Chief Investigator, Transport Safety (Vic).
The measurements from the post-incident survey were verified as accurate. The geometry at the site had not altered since the August 2009 survey. At that survey, road and track bearings were made using range/bearing binoculars that were subsequently found to produce inconsistent readings due to magnetic influence and battery condition.[11]
Sighting requirements
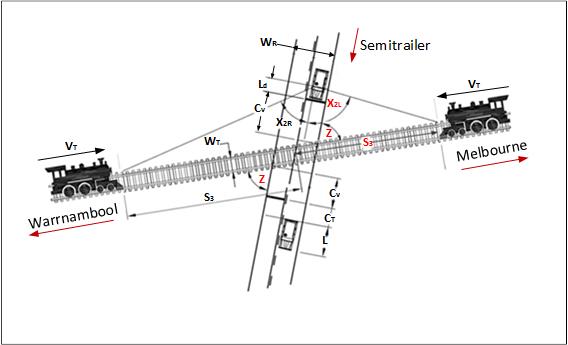
AS 1742.7:2016 specified the definitions, methodology and formulae for calculating the sighting distance required by a driver of a road vehicle stopped at a crossing (Figure 9).
Figure 9: Sighting distances and angles as defined in AS 1742.7:2016
The diagram shows the definition of key geometric features including the acute angle between track and road (Z), the viewing angle from the driving cab (X2L) and the sighting distance along the track (S3).
Source: Based on Figure D2 in AS 1742.7:2016, Appendix D and modified by Chief Investigator, Transport Safety (Vic)
The calculated sighting distance along the track (S3) was designed to ensure sufficient time for a vehicle to start from stop and clear a crossing before the arrival of a train
Using the assumptions contained in the Australian Standard for a vehicle of the maximum length allowed for this road (design vehicle),[12] the calculated required sighting distance for such a vehicle stopped on the north side of the Phalps Road level crossing was 537 m. For a vehicle with similar specifications to the accident vehicle, the calculated sighting distance requirement was 508 m.
To achieve the required sighting distance of 537 m looking to the driver’s left, the required sighting angle (X2L) was 116 degrees (Figure 9). This exceeded the maximum of 110 degrees, specified in the Australian Standard, for level crossings protected by passive controls.[13]
Of note, the driver of the incident vehicle could not see to an angle of 110 degrees from the forward direction of the truck cab. In this and similar cab configurations, a driver may be limited to an angle of between 100 to 110 degrees. The Standard may therefore not fully reflect the limitations that may exist with some cab configurations.
When outside a vehicle, there was a clear view along the track (Figure 10).
Figure 10: The view to the track when not encumbered by the road vehicle structure
The image shows the view from Phalps Road along the track in the east. When not restricted to the specified maximum viewing angle, or the structure of the road vehicle, the view along the track exceeded 500 m.
Source: Chief Investigator, Transport Safety (Vic)
Assessment of hazards and risks at Phalps Road level crossing
Australian Level Crossing Assessment Model (ALCAM) survey
ALCAM background
The Australian Level Crossing Assessment Model (ALCAM) was the primary tool for collecting information on each level crossing in Victoria. ALCAM is an assessment tool used to identify hazards and risks at level crossings, and to assist the prioritisation of level crossing upgrade. The project to establish ALCAM commenced in 1999 and was overseen by a committee of representatives from Australian states and territories and New Zealand.
In 2003, the Australian Transport Council (ATC) and the Standing Committee on Transport (SCOT)[14] Rail Group agreed that ALCAM be adopted nationally. In Victoria, the collection and assessment of level crossing data was managed by VicTrack.[15]
Since it was first developed, there have been several modifications made to ALCAM and its risk methodology. The initial model determined a Risk Score that was a measure of the risk posed to each driver approaching a crossing. Exposure in terms of train and road traffic volumes was not directly incorporated into this score, but rather considered when assessing a crossing’s score against limit scores for installation (new crossings) and intervention (existing crossings).
About 2008, significant changes were made to the model’s treatment of exposure with the intention to achieving alignment with the risk management standard AS/NZ4360. An Exposure Factor equal to the product (VxT) of road traffic volume (V) and train traffic volume (T) was incorporated as a multiplier in the Risk Score. This change resulted in substantial re-ordering of the ALCAM-based level crossing upgrade priority list, with a stronger emphasis towards upgrading crossings with high volumes of road and rail traffic. Crossings with low traffic generally moved lower on the priority list.
Release of revised ALCAM in 2014
In 2014, further modifications were made to the ALCAM model. A review commissioned in 2011 found that the (VxT) approach used for exposure did not best replicate the observed collision record, nor adequately consider the effect of the type of crossing on the collision rate. As a result, the ALCAM Exposure Factor was modified using new algorithms. In addition, methodologies for the Infrastructure Factor and Consequence Factor were also updated and a substantially revised ALCAM model released in November 2014 (Figure 11). This had the effect of a further re-ordering of the ALCAM-based level crossing priority list.
Figure 11: ALCAM risk score as defined in the model released in November 2014
ALCAM Risk Score = Infrastructure Factor X Exposure Factor X Consequence Factor
Where the Infrastructure Factor X Exposure Factor = Likelihood
Source: ALCAM in Detail, An introduction to the new ALCAM models (2014), 6 May 2015
The revised ALCAM model was validated by February 2015. The performance of the model was tested using observations of its general behaviour against expected risk factors and statistical comparisons with incident history. The report concluded that the scoring gave due weight to the risk factors known to cause incidents and allowed for the greater consequence known to be possible when certain combinations of factors come into play, such as high speed passenger trains and heavy vehicles. Further, the new ALCAM model was found to perform well against references and to be appropriate for its current use as a level crossing risk assessment tool.[16]
In addition to its risk rating system, ALCAM used flags to highlight specific characteristics or risks that may result in an unacceptable situation, such as queuing, sighting and short stacking. ALCAM flagged areas for further assessment and non-compliance with the requirements of AS 1742.7.
ALCAM assessment of Phalps Road level crossing
Prior to this incident, the most recent ALCAM survey of the Phalps Road level crossing was in August 2009. This assessment identified that there was insufficient sighting to the left of road users when stopped at the crossing. It estimated an S3 sighting distance of 61 m (when stopped to the north) and 63 m (when stopped to the south), compared to the required sighting distance of over 500 m. The S3 measurements were made using the maximum permitted sighting angle (X2L) of 110 degrees.
In 2008, the Phalps Road level crossing had a priority ranking of 217[17] in the State’s list of passive level crossings. A risk ranking report run on 6 July 2016 using the revised (2014) ALCAM methodology showed the crossing was ranked 103.
Contracted level crossing assessment in 2014
In 2014, V/line engaged a contractor to undertake a review of several passively protected level crossings including the Phalps Road crossing. The review included identifying hazards and potential controls but did not include an assessment against V/Line’s safety obligations.
The contractor’s review of the Phalps Road level crossing identified that it did not meet the sighting distance required by AS1742.7-2007.[18] The contractor explored a number of treatment options with the Colac Otway Shire Council including road closure, restricted access and road realignment. The contractor, V/Line and the Shire Council also conducted a joint site inspection in October 2014. The contractor reported that the Shire Council did not support the road treatment options. The outcomes of the contractor’s review and findings were provided to V/Line.
Additional V/Line sighting assessment in 2016
V/Line conducted a further line of sight assessment at the Phalps Road level crossing on 14 February 2016 that indicated that the S3 sighting requirements of the Australian Standard were met. This assessment was in error, as the S3 measurements that were made were not restricted to the maximum permitted sighting angle (X2L) of 110 degrees.
Level crossing safety coordination and decision to upgrade
V/Line – Colac Otway Shire Council interaction
Legislation[19] (2006) introduced the requirement for a safety interface agreement (SIA) between rail and road managers. This then took the form of a requirement for an interface agreement (IA) when the Rail Safety National Law commenced in Victoria in May 2014. ONRSR described the purpose of the interface coordination provisions of the Rail Safety National Law as ensuring rail transport operators and road managers identify risks to safety arising from rail or road crossings, determine measures to manage, so far as is reasonably practicable, those risks and seek to enter into interface agreements to manage the risks.
An SIA was endorsed by the Colac Otway Shire Council, V/Line and VicTrack in 2011.[20] This interface agreement listed the rail-road interface locations[21] within the Shire and required all parties to the agreement to undertake inspections and/or audits to identify risks and facilitate any required remedial action. The agreement stated that the parties were to ensure that a risk management process was established, implemented and maintained.
V/Line and the Colac Otway Shire Council (Shire Council) had met prior to this formal agreement. In July 2009 and following a review of level crossings in the district, V/Line recommended to the Shire Council that several level crossings, including the Phalps Road level crossing, be realigned or closed. The Shire Council expressed the opinion that it was difficult to close this crossing, as it provided access between farms and the Princes Highway. The Shire’s preferred option was to upgrade the crossing to active protection. V/Line opined that closure was their preferred option and that it would be some years before the crossing would be upgraded due to the light vehicle traffic on the road.
The Victorian Railway Crossing Safety Steering Committee (VRCSSC) was established in 2005 under section 36 of the Transport Act 1983 (Vic) to advise and make recommendations to the Minister of Transport on policy, management and standards for road and pedestrian crossings in Victoria. The VRCSSC had four sub-groups: the Railway Crossing Technical Group (RCTG); the Railway Crossing Human Factors Group (RCHFG), the Railway Crossing Safety Awareness Group (RCSAG) and the Rail Crossing Project Delivery Group (RCPDG).
The RCPDG was responsible for delivering the government’s program of level crossing upgrades. The group was chaired by VicTrack and its membership included Public Transport Victoria (PTV), road authorities, rail operators and rail infrastructure managers. The rail regulator, Transport Safety Victoria (TSV), was an observer to this group.
Phalps Road upgrade
In February 2015, the VRCSSC endorsed a new 4-year Better Roads for Regional Communities – Road Level Crossing Program (2015-2019) that had been submitted by the RCPDG. The new program included the upgrade of the Phalps Road level crossing to active protection.
Documentation supporting the upgrade proposal indicated that there had been three reported near-collisions at the Phalps Road level crossing.
Regulatory oversight of level crossing safety management
2013 compliance inspection of V/Line by Transport Safety Victoria
Prior to May 2014, the rail safety regulator in Victoria was Transport Safety Victoria (TSV) operating under the statutory authority of the Director, Transport Safety.[22] Following a collision at a passively protected level crossing in September 2013,[23] TSV conducted a rail safety compliance inspection of V/Line. The key audit finding was that TSV was unable to determine whether V/Line was ensuring the safety, so far as is reasonably practicable (SFAIRP),[24] of passive railway level crossings without assessing the risk specific to each crossing. The final inspection report was issued to V/Line on 14 April 2014. In its cover letter, TSV advised V/Line that TSV was not entirely satisfied with the adequacy of the safety management of passive level crossings and flagged an intention to look further into the issue. The finding was closed within the TSV audit and compliance system, and a Projected Compliance Activity Plan (PCAP) raised as a trigger for future audit activity.
V/Line responded to the inspection report on the 28 April 2014, stating that it believed it was managing the risk SFAIRP. V/Line argued that substantial work had been completed on the management of safety risks at passive level crossings and advised of further site-specific assessments on a prioritised basis.
Transition to Office of National Rail Safety Regulator
On 19 May 2014, the regulation of rail transport in Victoria transitioned from TSV to the Office of the National Rail Safety Regulator (ONRSR). From that point, ONRSR became the agency responsible for rail regulation in Victoria, supported in day-to-day regulatory functions by TSV under a Service Level Agreement.
The outcomes of the September 2013 compliance inspection of V/Line, together with the inspection report, was provided to ONRSR on 16 April 2014. In response, ONRSR advised TSV that it was developing a policy position on level crossings, and that ONRSR expectations around risk assessment of level crossings would be considered as part of that process.
ONRSR has advised that it took, and continues to take, a risk-based approach to its regulatory effort. In practical terms, ONRSR advised its focus was on those issues that presented the highest overall risk and its resources were allocated to achieve the greatest safety benefit.
From the time regulatory oversight changed to ONRSR in May 2014, to the time of this occurrence on 13 July 2016, ONRSR regulatory activity regarding level crossing safety was focussed primarily on crossings with active protection that ONRSR advised presented a higher overall risk than passive level crossings. ONRSR advised that during this period Victoria had a number of significant incidents involving active level crossings that required their sustained attention. Regarding passive crossings, ONRSR advised liaising with V/Line on its management of risks associated with corrosion of buried rail,[25] and conducting post-incident compliance inspections at Dunbar Road, Merrigum in June 2016. ONRSR did not engage with V/Line on its risk assessment of passive level crossings, the matter raised with ONRSR in April 2014 following TSV’s compliance inspection of V/Line.
Road vehicle
The road vehicle was a 2013 Kenworth K200 ‘cab-over-engine’ prime mover (Figure 12) that was hauling a semi-trailer. The overall length of prime mover with trailer was about 14.6 m.[26]
The vehicle was certified to Australian Design Rules (ADR) 64/00 standard for Road Train and/or B-Double use and was fitted with an ADR compliance plate. Maintenance was up-to-date.
ADR 42/04 – General Safety Requirements also applied to this prime mover. It specified that a motor vehicle must not be constructed or equipped in such a manner as to prevent the driver from having an adequate view of traffic on either side of the vehicle and in all directions in front of the vehicle to enable the vehicle to be driven safely. There was no detail in the design rules on a required viewing arc rearward of ‘either side’ of the vehicle.
Figure 12: A similar Kenworth prime mover to that involved in the collision
Source: Kenworth Trucks
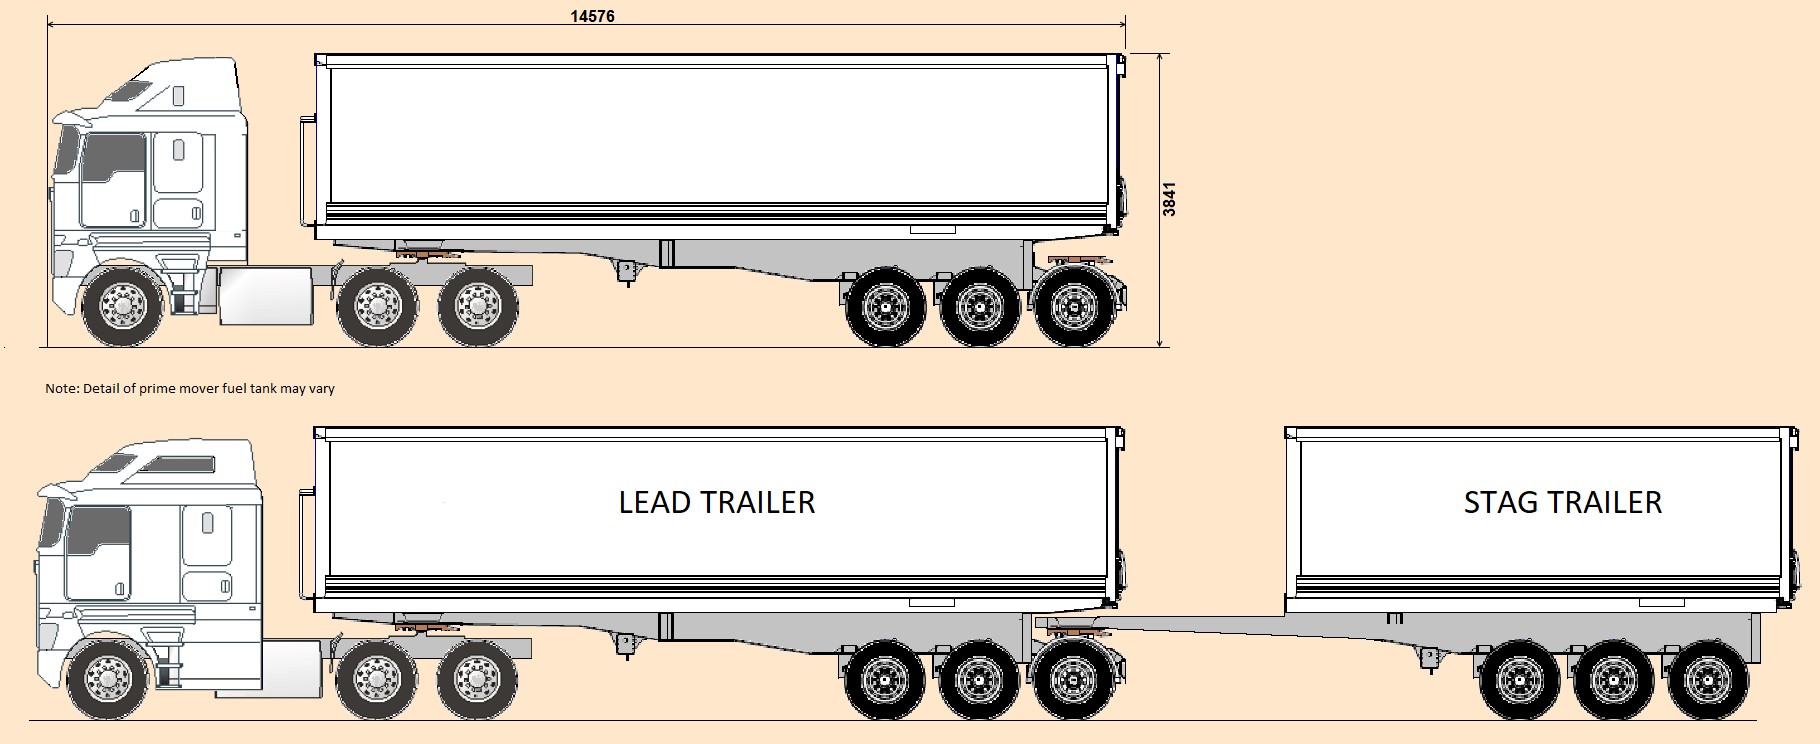
At the time of the collision, the truck was running in a semi-trailer configuration with stag trailer removed (Figure 13). Its semi-trailer was loaded with 26.5 t of Canola meal giving the truck a total mass of approximately 45 t.
Figure 13: Schematic of truck in semi-trailer configuration and with stag trailer
Source: Adapted by Chief Investigator, Transport Safety (Vic)
Previous incidents at level crossings with acute road-to-rail angle
Trawalla 2006
On 28 April 2006, a Diesel-Multiple-Unit passenger train collided with a semi-trailer on the Ercildoune Road level crossing near Trawalla, about 40 kilometres west of Ballarat. The train was derailed and two persons sustained fatal injuries.
Ercildoune Road was an acute-angle level crossing with passive protection (Stop signs). The road-to-rail angle to the truck driver’s left was about 52 degrees. There is no public report with detailed findings.
Lake Charm 2013
On 12 February 2013, a locomotive-hauled passenger train collided with a semi-trailer on the B. McCann Road level crossing near Lake Charm, in northern Victoria. There were no injuries.
The level crossing was equipped with Give Way signs. The angle between the truck’s direction of approach and the railway line to the truck driver’s left was about 65 degrees. The ATSB investigation[27] into the incident found that the truck driver’s view to the left along the track was restricted due to the acute angle.
Following the collision, the road was ‘squared up’ to the railway, and the level crossing added to the Safer Country Crossings program for upgrade. The crossing was subsequently upgraded in 2017.
Regulatory response to these events
Transport Safety Victoria advised that there was no specific audit or inspection activities initiated following the Trawalla (2006) or Lake Charm (2013) level crossing collisions. __________
The truck was travelling south along Phalps Road towards the level crossing at the same time that the passenger train was approaching from the east. Data from the truck and train were used to estimate the timelines for the approach of each vehicle to the point of collision.
When the truck initially stopped at the crossing, the train was more than 300 m away. The truck commenced moving towards the track when the train was between 220 and 260 m from the crossing. While the truck was stopped, the train was beyond the truck driver’s view through the truck’s passenger-side window.
Unaware that there was a train approaching beyond his line of sight, the truck driver proceeded to enter the level crossing. The driver heard the train’s horn shortly before the locomotive impacted the truck’s semi-trailer. The data suggests that the driver may have attempted to accelerate the truck just prior to impact. The truck driver did not hear the first sounding of the locomotive horn nor the commencement of the second sounding when the train was 178 m away, probably due to noise within the cabin of the prime mover and a closed passenger-side window.
There was no evidence to suggest that the truck driver was fatigued or that in-cab distractions influenced his ability to observe the train. The driver was unfamiliar with this crossing. In hindsight, he may have taken additional steps to improve his view by angling the truck cab further left. However, there was also no advice provided at the crossing that may have prompted or guided this behaviour.
The train was travelling within the permitted line speed and the locomotive driver took appropriate actions by sounding the horn and making an emergency brake application. The first horn was sounded prior to the whistle board at 400 m, however this was not considered a factor in this event.
Restrictions to viewing train
Road-to-rail angle and driver viewing angle
When stopped at a level crossing, the ability of a road user to see along the railway track to their left can be affected by in-cab obstructions. Crossing design considered that viewing in this direction may be restricted. AS 1742.7:2016 specified that when stopped at a Stop sign, the viewing angle for a driver looking to their left should not exceed 110 degrees from the straight-ahead direction.[28] The standard specified that if this angle is exceeded, passive level crossing controls shall not be used.
For a road vehicle stopped on the northern side of the Phalps Road level crossing, the viewing angle to achieve the required sighting distance was 116 degrees,[29] which exceeded the specified maximum viewing angle of 110 degrees.
View through truck’s passenger-side window
Post-incident sighting trials utilising the same model prime mover as that involved in the collision were conducted on the northern approach to the Phalps Road level crossing. The purpose was to gain a better understanding of the potential restrictions to viewing to the left from the driving cab. The prime mover was stopped aligned with the road direction, and with the front of the cab 10 m back from the track centreline.
The general finding of the trials was that the view along the track was restricted by the structure of the cab, and the absence of windows rearward of the driver (Figure 14).
Figure 14: The restricted view along the track with the truck stopped 10 m from the track
The image shows a typical view from the truck driving position, taken during the trials. It shows a severely restricted view towards the track. The view is limited tothe size and location of the cab’s passenger-side window.
Source: Chief Investigator, Transport Safety (Vic)
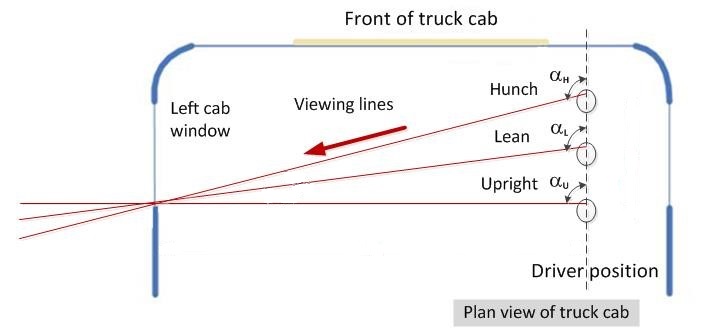
With the truck at its stopped location, achievable sighting distances (along the track to the left) and the viewing angles (of the driver towards the track) were determined using laser measuring equipment. The measurements were taken for the driver upright (αU), leant forward (αL) and hunched forward (αH) (Figure 15).
Figure 15: Plan view showing driver viewing angles for a range of driver postures
Source: Chief Investigator, Transport Safety (Vic)
For these three driver positions, the achievable sighting distances ranged from 29 to 60 m, and the achievable viewing angle from 90 to 104 degrees (Figure 16). The maximum distance and viewing angle achieved were with the driver hunched forward over the steering wheel. The rear edge of the passenger-side window was the limit of the view towards the track.
Figure 16 Viewing angles and sighting distances with the truck about 10 m from track
Sighting angle and distance measurements from three driving postures
Position
Angle (α)
Sighting distance
Upright
90°
29 m
Lean
96°
46 m
Hunched
104°
60 m
The table summarizes the measured viewing angles and sighting distances achieved from the driving cab during trials.
Source: Chief Investigator, Transport Safety (Vic)
Implications of the restricted view
The extent to which the driver of the incident truck leant forward to look for trains, or may have squared his driving cab towards the track[30] to improve the view, is uncertain. However, based on the post-incident measurements and available evidence, it is very probable that when stopped and looking left through the passenger window, the driver’s view was restricted. This restriction was a consequence of the acute road-to-rail angle at this location and the design of the truck’s cab. Similar sighting restrictions would exist for other vehicles not fitted with passenger-side windows rearward of the driving position or a rear window in the cab.
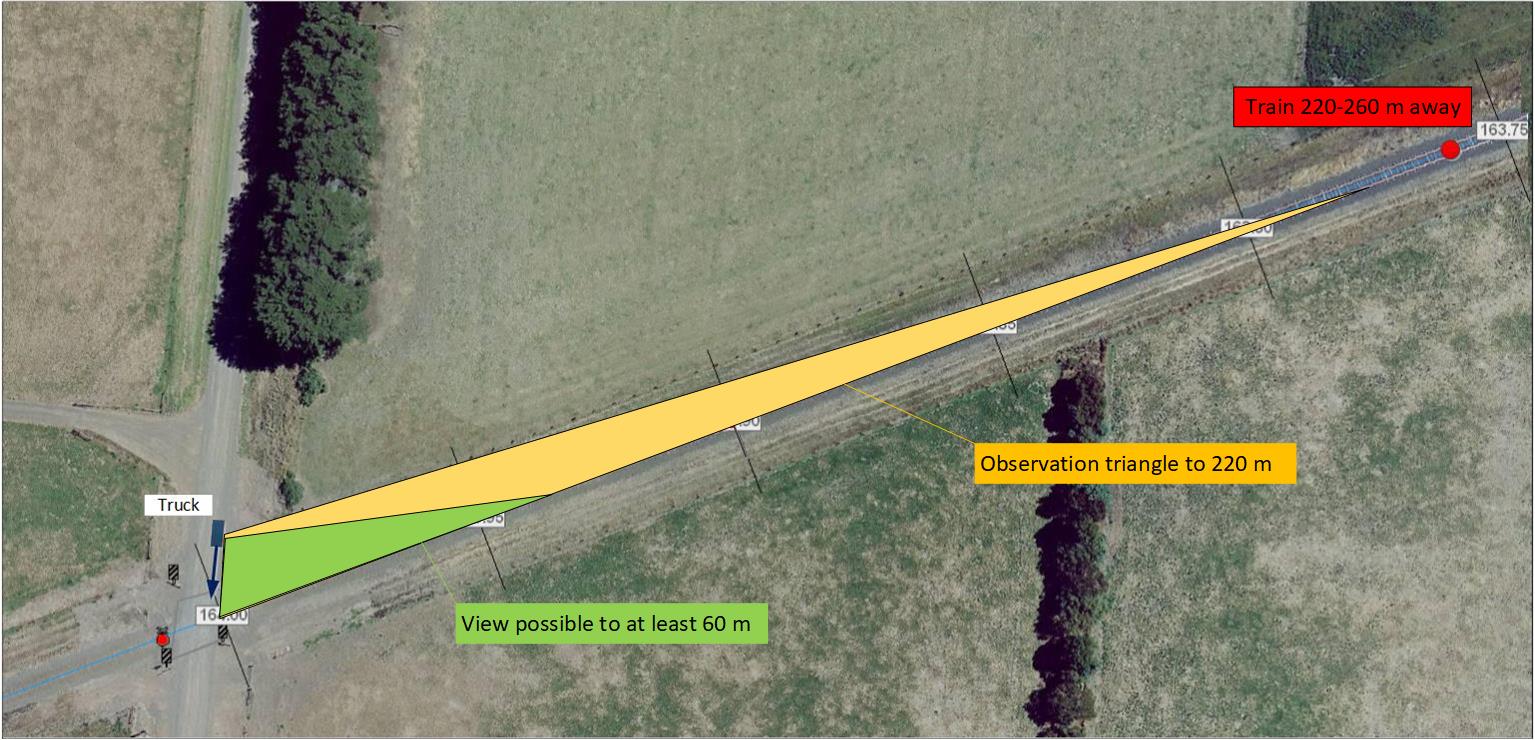
The implications of the restricted view was that the driver did not observe the approaching train when stopped prior to moving towards the crossing. The view along the track was significantly less than that required to observe the train, probably at least 60 m but no further than 220 m (Figure 15).
Figure 17: The position of the train when the truck started moving towards the crossing.
The figure is an aerial view of the level crossing and the track to the crossing’s east. The figure depicts the estimated position of the train at the time the truck started moving from its stopped position, the minimum distance of 60 m that the truck driver could probably see, and the observation triangle to a distance of 220 m. The train was 220-260 m from the crossing, and is shown at 240 m.
Source: Pass Assets, Public Transport Victoria, annotated by Chief Investigator, Transport Safety (Vic)
Risk management of the Phalps Road level crossing
Decision to upgrade
The ALCAM risk ranking was not sufficient to have this crossing prioritised for upgrade within the 4-year program of 29 passive crossing upgrades. Its elevation was in response to three reported near-collision incidents. In addition, there had been long-term discussions between V/Line and the Shire Council regarding the sighting deficiencies at the crossing. The decision to upgrade the Phalps Road level crossing was endorsed by the VRCSSC in February 2015.
Managing risk so far as is reasonably practicable
The Rail Safety National Law (RSNL)[31] applied to the management of risk and safety at the Phalps Road level crossing. Under rail safety national law, duty holders are required to eliminate risks so far as is reasonably practicable (SFAIRP); and if it is not reasonably practicable to eliminate risks to safety, to minimise those risks SFAIRP. In this case, as the crossing was not closed and the risk eliminated, then the risks would need to be minimised SFAIRP.
The Office of the National Rail Safety Regulator (ONRSR) established under the RSNL provided guidelines[32] on the background, intent and application of the concept of SFAIRP. The guidance points out that although what is reasonably practicable is ultimately assessable by a court of law, that in minimising risks SFAIRP, duty holders would need to consider:
the likelihood of the hazard or the risk concerned occurring;
the degree of harm that might result from the hazard or the risk;
what the person concerned knows, or ought reasonably to know, about the hazard or risk, and ways of eliminating or minimising the risk;
the availability and suitability of ways to eliminate or minimise the risk; and
after assessing the extent of the risk and the available ways of eliminating or minimising the risk, the cost associated with available ways of eliminating or minimising the risk, including whether the cost is grossly disproportionate to the risk.
Available risk controls not deployed
The sighting deficiencies due to the acute road-to-track interface at the Phalps Road level crossing were identified in the ALCAM survey of 2009 and were discussed between the V/Line and the Colac Otway Shire Council from that time. Further site assessments in 2014 confirmed the sighting issues. However, available controls were not applied to the level crossing even though the hazards were known. There was an opportunity for V/Line and/or Colac Otway Shire Council to implement available risk controls prior to and after the decision to upgrade.
Interface agreement
Management of the risks associated with level crossings is a shared responsibility between rail and road managers. An interface agreement (IA)[33] between V/Line and the Colac Otway Shire Council existed and provided a basis for dialogue and risk management of the Phalps Road level crossing. Active dialogue had commenced in 2009 and a formal interface agreement signed in 2011.[34]
Even though an interface agreement existed, it was not an effective mechanism for achieving timely safety outcomes. All parties to the agreement were aware of the sighting issues at the Phalps Road level crossing for at least seven years prior to the collision. However, their interaction was ineffective at addressing the identified level crossing hazards.
Limitations of the interaction between road and rail managers included the difficulty in achieving an agreed position on timely risk treatments. The rail and road managers had competing operational and resource priorities that led to an impasse on what actions should be taken and by whom, and as a result level crossing upgrade became the default solution.
Network exposure to acute-angle crossings
Acute-angle crossings
A driver typically needs to be able to look parallel along a track to check for approaching trains. Therefore subtracting the AS1742.7:2016[35] maximum viewing angle (to the left) of 110 degrees from 180 degrees gives a nominal minimum road-to-track crossing angle (Z in Figure 9) of 70 degrees. Crossings with an acute interface angle (to the left) of 70 degrees or greater would typically comply with the viewing angle requirement of the standard and those with lower values would generally not meet the standard.
At the time of this incident, there were a reported 166[36] passively protected level crossings (35 at intersections of passenger lines and public roads) in the V/Line regional network[37] with a road-to-track interface angle to an approaching driver’s left of less than 70 degrees,[38] and therefore unlikely to comply with the Australian Standard specified maximum viewing angle of 110 degrees. There were also a further 76 level crossings with left-side road-to-track angles of between 70 and 80 degrees. Based on the measured maximum viewing angle of 104 degrees from a prime mover similar to the incident truck, some of these crossings may also have restricted viewing from some types of road vehicle.
Strategy used for managing network exposure to acute-angle crossings
ALCAM was the primary tool used to evaluate level crossing risk in Victoria. The methodology used to evaluate the ALCAM risk score has changed significantly since the model was first introduced. This has meant that the ALCAM system of prioritisation has also changed over time. Prior to the 2014 model update, the prioritisation was excessively weighted toward crossings with higher traffic volumes. This may have contributed to a reduced safety focus on regional passive level crossings with low traffic, including those crossings with acute road-rail angles.
Following further review of the model’s methodology, there was a new release in 2014 that validation has showed improved correlation between risk score and incident history. The supporting ALCAM guidelines[39] to this release described ALCAM as a comprehensive tool for the assessment of level crossing hazards.
Consistent with ALCAM guidelines, collision, and near-collision, data was also analysed by the Rail Crossing Project Delivery Group (RCPDG) to moderate the ALCAM-based priority list. Incident data provided an additional indicator of the likelihood of an event and was used in conjunction with ALCAM prioritisation to identify a final listing of those crossing proposed for upgrade. The committee process was then the final filter used to arrive at those crossings listed and approved for upgrade in any given program cycle.
ALCAM flags for hazards and non-compliance
To support risk assessment and treatment processes, ALCAM also identified particular hazards at level crossings for consideration regardless of the overall ALCAM Risk Score. Flags were used to highlight specific characteristics or hazards (such as queuing, sighting and short stacking). The ALCAM system also included flags indicating non-compliance with the Australian Standard.
ALCAM guidelines stated that ALCAM did not attempt to define a ‘safe’ or acceptable level of risk. It also provided the guidance that any risk assessment and treatment also needed to consider other factors, including:
Collision and near-collision history
Engineering experience (both rail and road)
Local knowledge of driver or pedestrian behaviour
Social and economic assessment
Standards and international best practice.
However, other than collision and near-collision history being considered for upgrade prioritisation, there was no evidence of broad and consistent consideration by V/Line of the other factors identified in the ALCAM guidelines. In addition, the ALCAM Australian Standard non-compliance flags were not used as a trigger for prioritising action by either the rail or road managers.
The high cost of upgrade from passive to active protection meant that a limited number of passive crossings on the V/Line regional network were upgraded each year. The 2015-19 Better Roads upgrade program scheduled 29 upgrades from passive to active protection over the four year period, equating to about seven crossings per year. Based on the number of acute-angle passive crossings on the regional network, and this rate of upgrade, a considerable number of passively protected crossings continued to have restricted sighting due to an acute road-to-track interface.
It is probable that the low traffic volumes at many of these crossings led them to be assessed as low risk and other available risk treatments were not deployed.
That many of these untreated acute-angle passive crossings were on passenger rail corridors also increased risk to the travelling public. Between 2006 and 2016 there were three collisions[40] between heavy transport (trucks) and passenger trains at acute-angle crossings with restricted sighting to the road user’s left.
Other available controls for managing this risk
Grade separation and upgrade to active protection are effective risk controls for acute-angle level crossings. However, cost and the annual rate of upgrade means that other risk treatments should be considered for low-use acute-angle passive crossings in regional areas (Figure 18).
Figure 18: Other potential risk treatments at acute-angle level crossings
Control
Potential outcome
Potential barriers
Closure of crossing
Risks eliminated.
Community resistance due to the loss of a road access.
Road realignment
Compliance with AS1742 and reduction in hazard and risk.
Feasibility and cost will vary from site to site. May require land acquisition.
Rail speed restrictions
Reduction in hazard and the consequence of a collision.
Impact on passenger service delivery (timetables). Less impact on freight lines.
Alternative forms of active protection with lower cost[41]
Reduction in hazard and risk.
May not meet same standards as full active protection.
Exclusion of heavy vehicles from transiting crossing
Reduction in hazard and risk.
Restricted access for some vehicle types.
Systems that require users to seek permission to cross[42]
Reduction in hazard and risk.
Reduced ease of crossing use.
Source: Chief Investigator, Transport Safety (Vic)
Depending on site-specific characteristics, these risk treatments might be applied as long-term risk control measures, or to assist the management of risk pending an upgrade to active protection.
Regulatory oversight of management of passive level crossings
A compliance inspection of V/Line by TSV in late 2013 concluded that V/Line was rarely assessing passive level crossings on a location-by-location basis and, as a result, TSV was unable to be satisfied that risks were being managed so far is reasonably practicable (SFAIRP). V/Line responded that they believed that they were managing the risk SFAIRP and that a program of level crossing inspections was scheduled.
ONRSR was advised of the key finding of the compliance inspection shortly before the transition to national rail regulation in Victoria in May 2014. From May 2014 to the occurrence in July 2016, ONRSR did not engage with V/Line on the concerns raised by TSV in April 2014. ONRSR advised that it had taken (and continues to take) a risk-based approach to determine its regulatory effort. It described the application of a systematic decision making framework that prioritises regulatory activity and informs decision outcomes based on an assessment of risks to rail safety.
ALCAM surveys in 2009
The ALCAM survey of the Phalps Road level crossing in 2009[43] contained inaccuracies in bearing measurements of up to 41 degrees. This significantly exceeded the ALCAM Crossing Assessment Handbook (of that time) that specified a measurement precision to the nearest 5 degrees.[44] The bearings were taken using bearing/range finding binoculars that were subsequently replaced by the surveying firm due to inaccuracies with this measurement equipment.
At the Phalps Road level crossing, the measurement errors resulted in an estimated acute road-to-rail angle 7 degrees less than actual. This measured value resulted in a worse scenario that the actual configuration and the survey error at Phalps Road had no consequence.
However, errors due to using this survey equipment at other locations remained latent within the ALCAM database.
From the evidence available, the following findings are made with respect to the collision between a truck and semi-trailer and V/Line passenger train 8753 at the Phalps Road level crossing at Larpent Victoria on 13 July 2016. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
The truck driver entered the Phalps Road level crossing unaware that there was an approaching train beyond his line of sight.
For southbound road traffic approaching the Phalps Road level crossing, the view along the track to the left was restricted due to the acute road-to-rail angle.
Available risk controlsto manage the risk posed by known sighting deficiencies at the Phalps Road level crossing were not deployed by V/Line or the Colac Otway Shire Council.[Safety Issue]
The interaction between V/Line and the Colac Otway Shire Council wasineffective at addressing identified sighting issues at the Phalps Road level crossing. [Safety Issue]
Other factors that increased risk
More than 100 level crossings in the V/Line regional rail network(including 35 at the intersection of passenger lines and public roads)were non-compliant with the left-side viewing angle requirements of AS 1742.7:2016. These crossingshad an acute road-to-rail angle that affected the ability of drivers to sight trains approaching from their left. [Safety issue]
V/Line’slevel crossing assessment processes did not result in deployment of available risk controls at many passively protected acute-angle level crossings. [Safety Issue]
From May 2014 to the occurrence in July 2016, ONRSR did not engage with V/Line on its approach to risk assessment of passive level crossings, the matter raised with ONRSR by TSV in April 2014. Regulatory resources were directed to other safety priorities.
Errors remained within the ALCAM database due to the type of equipment used to measure road and rail bearings during ALCAM surveys in 2009. [Safety Issue]
Other findings
The handling of the train did not contribute to the collision.
The truck driver stopped at the crossing and attempted to observe for trains.
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the rail industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: Available risk controls to manage the risk posed by known sighting deficiencies at the Phalps Road level crossing were not deployed by V/Line or the Colac Otway Shire Council.
Safety issue description: The interaction between V/Line and the Colac Otway Shire Council was ineffective at addressing identified sighting issues at the Phalps Road level crossing.
Risks at other acute-angle level crossings on network
Safety issue description: More than 100 level crossings in the V/Line regional rail network (including 35 at the intersection of passenger lines and public roads) were non-compliant with the left-side viewing angle requirements of AS 1742.7:2016. These crossings had an acute road-to-rail angle that affected the ability of drivers to sight trains approaching from their left.
Risk assessment and deployment of available risk controls
Safety issue description: V/Line’s level crossing assessment processes did not result in deployment of available risk controls at many passively protected acute-angle level crossings.
Safety issue description: Errors remained within the ALCAM database due to the type of equipment used to measure road and rail bearings during ALCAM surveys in 2009.
Additional safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
The Victorian Level Crossing Safety Steering Committee (VLCSSC) has established a Passive Crossing Working Group. Of relevance to this report is work around low cost technologies, and an action to explore the option of including the details of ‘limited sighting’ crossings on the VicRoads heavy vehicle road network maps.
General details
Train details
Train operator:
V/Line Pty Ltd
Registration:
8753
Type of operation:
Passenger service
Persons on board:
Crew – 3
Passengers – 99
Injuries:
Crew – 2
Passengers – 18
Damage:
Substantial
Road vehicle details
Vehicle type:
Prime mover and semitrailer
Registration:
Private
Persons on board:
Driver – 1
Injuries:
Driver – 1
Passengers – 0
Damage:
Significant
Sources and submissions
Sources of information
The sources of information during the investigation included:
V/Line
Colac Otway Shire Council
VicTrack
The rail safety regulator
The truck company
The truck driver
The locomotive driver.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to V/Line and its level crossing contractor, VicTrack, Colac Otway Shire Council, TSV, ONRSR, the locomotive driver, the truck driver and the truck company. Submissions from those parties were reviewed and where considered appropriate, the text of the draft report amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
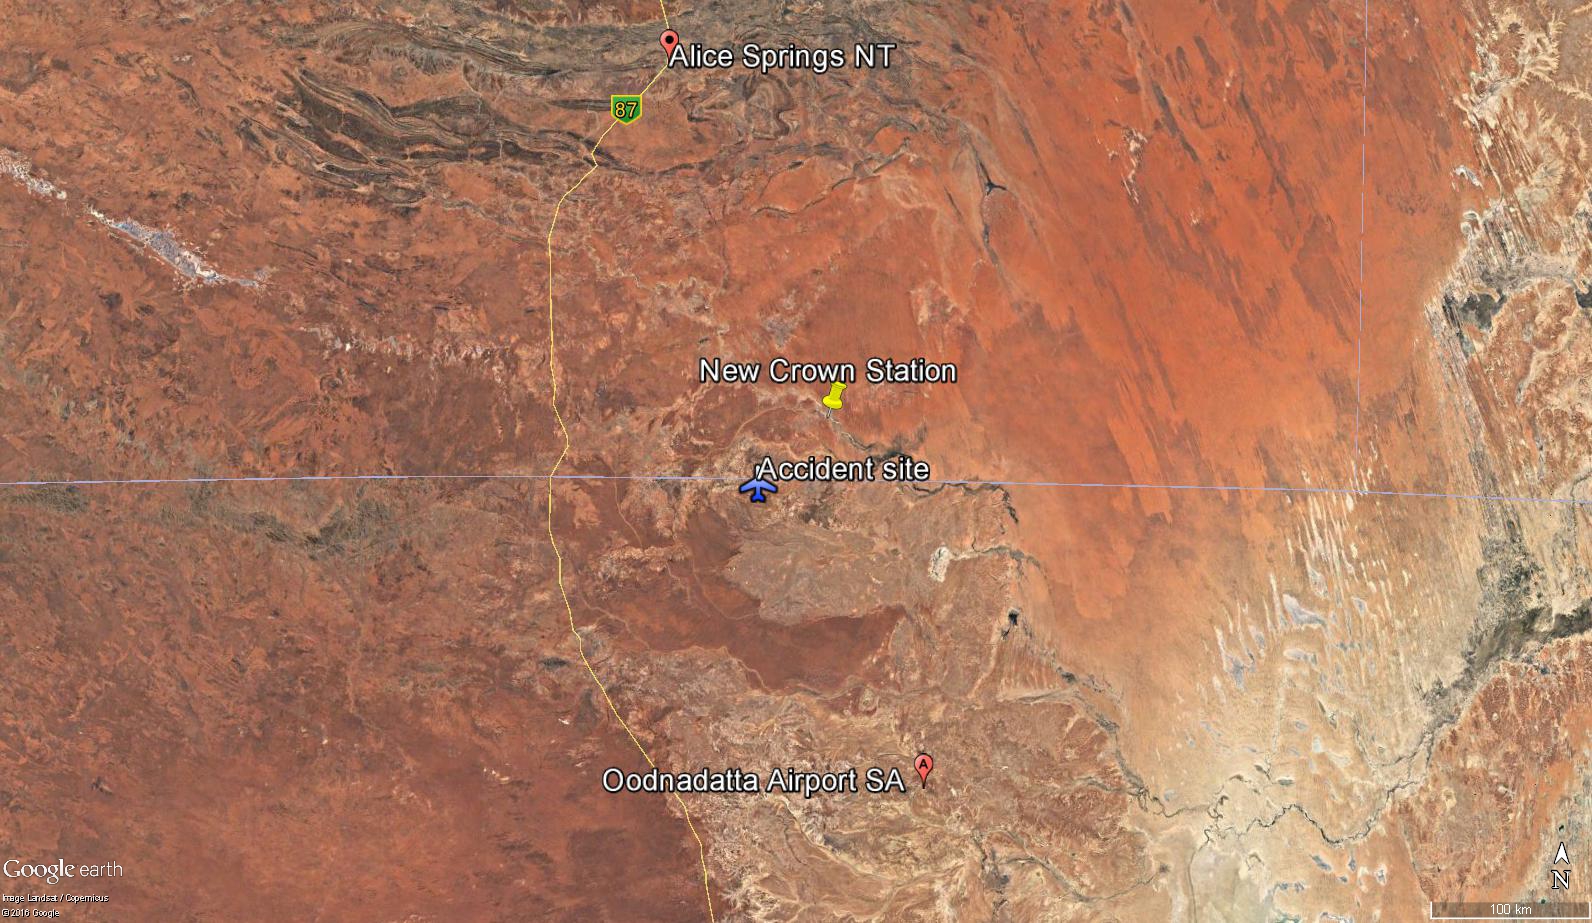
On 12 July 2016, the pilot of a Cessna 150 aircraft, registered VH-RXU, was conducting cattle spotting operations at New Crown Station, about 270 km south-east of Alice Springs, Northern Territory. The aircraft was observed conducting turning manoeuvres over the cattle at a reported altitude of about 500 ft.
A stockman recalled that, immediately preceding the accident, the pilot was directing them by radio to a breakaway herd of cattle in a nearby riverbed. The stockman observed the aircraft in a right turn moments before hearing it impact the ground, meters from their position.
For reasons that could not be determined, the pilot lost control of the aircraft and was unable to arrest the descent before the aircraft impacted the ground heavily. The pilot was the sole occupant on-board the aircraft and was fatally injured. The aircraft sustained significant damage.
What the ATSB found
The pilot lost control of the aircraft after commencing a right turn. While the actual events preceding the loss of control could not be concluded, the aircraft was likely operated at a slow airspeed with reduced stall margins. In the absence of other physical evidence, it was possible that control inputs made by the pilot induced a stall and incipient spin at an altitude that was not recoverable.
The pilot was not using the full lap/sash occupant restraint at the time of impact. The extent of injuries sustained by the pilot during the impact probably would have reduced if the sash portion of the restraint were used. This would likely have improved pilot survivability.
The fuel type used by the operator and pilot was not approved for use in VH-RXU. Although probably not contributing to the loss of control, it increased the risk of carburettor icing and formation of vapour in the fuel system.
What's been done as a result
The operator advised that since the accident, only the grade/type of fuel approved for use in the aircraft would be used.
Safety message
Turning manoeuvres at or close to the aircraft’s critical angle of attack, if mishandled, can lead to a stall that may result in the aircraft entering a spin. Recovery from this condition will take a considerable amount of altitude, dependant on the speed of response by the pilot and the use of appropriate control inputs.
Pilots need to assess the operational risks associated with not using full lap/sash restraints. The appropriate use of these restraints would prevent more serious deceleration injuries in the event of an accident.
To ensure engine performance, pilots and operators must ensure that the fuel used is of the correct grade/type for the aircraft, and is free of contaminants.
The occurrence
On 12 July 2016, the pilot of a Cessna 150 aircraft, registered VH-RXU (RXU), was conducting cattle spotting operations at New Crown Station, about 270 km south-east of Alice Springs, Northern Territory (Figure 1). At about 0700 Central Standard Time,[1] the pilot departed the property to a remote runway called Mosquito airfield, about 60 km to the south. On arrival, the pilot was reported to have discussed the morning’s operations with two groups of stockmen.
Figure 1: Accident site location
Source: Google earth modified by ATSB
The stockmen were tasked with conducting ground-based mustering activities using motorbikes. The pilot of RXU was to assist with locating the cattle and directing the two mustering groups toward them. The property owner stated that ground based mustering supported by aerial spotting was preferred, as it did not stress the cattle as much as aerial mustering.
It was reported that the pilot and stockmen commenced mustering/spotting activities a short distance to the north of Mosquito airfield at about 0730. The pilot was reported to have been operating between the two groups for some time before one of the stockmen noted the aircraft leaving the area. The stockman assumed that the pilot departed the area for Mosquito airfield to refuel.
The operator reported that the original plan was to use a Robinson R44 helicopter for the days mustering but it became unserviceable. The drum fuel positioned at Mosquito airfield was intended for use with the Robinson R44. Consequently, the operator expected the pilot would return to New Crown homestead to refuel during the morning. However, it was determined that the pilot refuelled using the drum fuel at Mosquito airfield instead.
The stockmen reported the aircraft appeared to be operating normally on resuming spotting operations. Further, the pilot, who was in frequent radio contact with the stockmen, did not report having trouble with the operation of the aircraft.
The pilot continued spotting and directing the stockmen to cattle along a thickly wooded creek bed when some cattle broke away from the main cattle herd. Soon after, the stockman unexpectedly exited the creek bed and sought direction from the pilot back to the cattle. The stockman recalled observing the aircraft flying away from them before it commenced a right turn back toward the cattle herd.
The stockman turned the motorbike around to re-enter the creek bed when seconds later a loud ‘bang’ was heard. The stockman stopped and immediately looked toward the direction of the sound, observing the aircraft to have crashed about 30 m away.
The stockman radioed that the aircraft had crashed and immediately proceeded to the aircraft. The pilot had sustained fatal injuries.
The pilot held a Private Pilot (Helicopter) and (Aeroplane) Licence and was qualified to fly the Cessna Aircraft Company C150G (C150) aircraft. The pilot was also endorsed on the Robinson R44 and R22 helicopter.
In 1998, the pilot completed a low-level safety course for which 10 hours flying was completed. The pilot did not hold a low-level flying or mustering endorsement, however, those endorsements were not required unless the aircraft was conducting spotting/mustering activities at an altitude lower than 500ft above ground level.
The pilot’s total aeronautical experience at the time of the accident could not be determined as the pilot’s logbooks were incomplete. The last recorded entry on 27 June 2016 indicated 2,676 total flying hours, of which 496 hours were on helicopters. The pilot’s logbook showed that from 1988, the pilot had predominantly flown single engine Cessna aircraft. The pilot last flew a C150 aircraft on the day prior to the accident, conducting aerial spotting operations.
Since obtaining a helicopter rating in 2014, the Robinson R44 helicopter was the primary aircraft flown. Although the operational characteristics of flying a helicopter would have differed from a fixed wing aircraft, there was no conclusive evidence that this adversely effected the pilot’s flying ability on the day of the accident.
A review of the pilot’s training records identified that the pilot had satisfactorily completed a biennial aeroplane flight review on 7 April 2014. The review was conducted under Civil Aviation Regulation (CAR) 1988, Part 5 in a Cessna 172 aircraft. Since that flight review, Civil Aviation Safety Regulation (CASR) Part 61 was introduced, and the pilot was overdue for a biennial flight review in accordance with those regulations.
On the day prior to the accident, while flying RXU, the pilot discontinued flying for the day after feeling a degree of motion sickness. The pilot reported this to the operator and discussed being more susceptible to motion sickness after having a medical procedure some years ago. The medical procedure was recorded in the pilot’s aviation medical file. A stockman and operator reported the pilot as appearing well on the morning of the accident.
The pilot held a valid Class 2 Aviation Medical Certificate with no restrictions.
Aircraft information
General information
The aircraft, VH-RXU, a C150, serial number 15066748, was manufactured in 1967 and entered the Australian register on 8 August 1968. The C150 is a single engine, all-metal, fixed tricycle-gear aircraft with a seating capacity of two.
Maintenance history
Review of the aircraft’s documentation showed it had a valid maintenance release with no open defects.
The aircraft logbooks show the last periodic inspection was conducted on 23 Sept 2015. At that time it had completed 6733.4 hours since manufacture.
The last periodic inspection identified some minor defects, which were rectified. Included in the maintenance tasks carried out during that inspection was the replacement of the seatbelts/lap sash occupant restraints and an airworthiness directive to test the stall warning system for which was certified as having no identified defects.
Meteorological information
Stockmen and ground crew operating in the area recalled the weather conditions as being fine with overcast cloud and a light to moderate breeze with some gusts. There were no ‘dust-devils’ reported in the area of operation.
Recorded meteorological information at Oodnadatta Airport, about 185 km to the south-east, indicated the temperature at 1130 was 13.0 °C. The wind was from the south-west at about 35 km/h and there was no recorded rain for the period. The area was under the influence of a high-pressure system with a recorded barometric pressure of 1023 hPa.
The elevation of the accident site was about 150 to 300 m above mean sea level.
While there were indications of light to moderate south-westerly winds with occasional gusts, the wind conditions were likely consistent with that experienced by the pilot during other in-flight manoeuvres. The wind was considered unlikely to have had an adverse effect the pilot’s ability to maintain control the aircraft during the right turn.
Wreckage information
Accident site
Photographic evidence provided to the ATSB indicated that the aircraft impacted the ground and slid approximately six meters before coming to rest upright, with the right-wing tip resting on the ground, and the left wing in the air. Despite significant damage, all major components remained attached to the aircraft, and the wreckage was not subjected to a post impact fire (Figure 2).
Figure 2: Photograph showing the accident site terrain and impact damage to the aircraft.
Source: SA police
Ground marks consistent with a left wheel and left-wing impact and sliding, was observed to the left of the wreckage. As a result of the ground impact, the pilot who was the sole occupant sustained fatal injuries.
There was no evidence of upward movement of the tailplane as would have been expected had the impact angle been steep. This indicates the aircraft’s nose impact angle was low (less than 45 degrees).
The left wing displayed a high level of impact damage to the lower outboard surface of the leading edge from the wing tip to approximately 1/3 its length (Figure 2). Crumpling and upward bending of the wing was evident behind the leading edge impact area and toward the wing root. It was probable that the left wing was part of the initial impact sequence of the aircraft. The right wing displayed significantly less damage, which was limited to the wingtip. Both wing fuel caps were in place and fuel seepage was observed from around the over-wing refill points.
Engine and propeller
From the evidence obtained from the accident site, there were no identified mechanical issues with the engine or propeller, that prevented normal operation of the aircraft. Bending and scratch marks on the propeller blades was consistent with the engine producing a level of power on impact.
Flightcontrols
The South Australia (SA) Police report indicated the control yoke was jammed in position. Operation of the ailerons, elevator, and rudder was not possible due to the impact damage. Continuity of the flight controls was not confirmed on-site. The flaps were in a partially extended position. The flap actuator extension was not measured, however, the flap indicator showed a position close to a 10-degree setting.
Fuel
On-site examination by the SA Police confirmed fuel was present in both aircraft wing tanks; however, the quantity could not be ascertained. The fuel appeared straw-coloured, and the samples taken did not show signs of particulate contamination. A combination of automotive unleaded fuel and aviation gasoline (Avgas) was identified in the fuel sample during testing. Traces of petroleum distillate were identified in the fuel samples. The operator indicated that no additives were used in the fuel. As such, the traces of distillate were considered fuel contamination. The fuel sample was identical to a drum fuel sample obtained from Mosquito airfield.
The operator advised that an unleaded fuel bulk storage tank was located at the homestead, and that the drum fuel supply at Mosquito airfield had been mixed with unleaded fuel and avgas in the ratio 2:1, (2 parts unleaded fuel to 1 part Avgas) to create a Mogas[2] variant. The operator advised that an Avgas drum fuel supply was sourced from a fuel distribution facility located at Alice Springs, and was normally used with the fixed wing aircraft.
Mogas utilisation
The operator advised Mogas was primarily used with the Robinson R44 helicopter but had been used in RXU on previous occasions. The C150 was capable of flying on Mogas fuel, with some countries providing approval for its use on the aircraft type. Where an Australian registered aircraft was to use Mogas, individual approval in the form of a supplemental type certificate was required. RXU did not have a supplemental type certificate issued for that purpose.
Due to variability of unleaded fuels used in Mogas, fuel volatility and susceptibility to carburettor icing and vapour locks was different from that of Avgas.
Carburettor icing
Mogas is generally higher in volatility than Avgas and will therefore absorb more heat from the mixing air when vaporising. This results in ice forming at higher ambient temperatures. As a consequence, the likelihood of carburettor icing while using Mogas is increased, with the onset of icing likely to occur at higher ambient temperatures and lower humidity than with Avgas.
Vapour lock
Vapour lock because of vaporisation of fuel is more critical with Mogas due to the increased volatility of the fuel. When engine shut down takes place, the engine compartment increases in temperature due to the sudden loss of cooling air flow and the thermal mass of the hot engine. If the engine is started shortly after, the fuel temperature in the engine compartment may be beyond its boiling point and therefore the risk of vapour lock is high.
A vapour lock in flight would result in an increased exhaust gas temperature, interrupted fuel supply, and rough running of the engine (similar to running too lean).
Survival aspects
In general, survival in the case of an aircraft accident depends on four separate aspects, the:
impact forces imparted on the aircraft occupants must be within human tolerance
occupants being restrained to prevent flail-type injuries
liveable space inside the aircraft being maintained
occupants having a means of escape.
Occupant restraints
The occupant restraints in RXU consisted of lap sash seatbelts. The seatbelts had a sash (shoulder) portion connected to the lap belt at an attachment buckle. The seatbelts were inspected by the SA police and were determined to be in a serviceable condition. Examination of the on-site evidence and injuries sustained by the pilot indicated the sash portion of the seatbelt harness system was not worn at the time of the accident.
Cessna aircraft information manuals recommended that for normal flight, the occupant adjust the harness tight enough to prevent excessive forward movement and contact with objects in the event of sudden deceleration. However, pilots sometimes disconnect or do not use the sash portion of the seatbelt harness during flight. This meant that the pilot’s upper torso was essentially unrestrained in the event of the aircraft decelerating quickly during an off-field forced landing, or impact with terrain.
The US National Transportation Safety Board published research paper SR 85-01 titled Impact Severity and Potential Injury Prevention in General Aviation Accidents. The paper highlighted the potential benefits of shoulder harnesses in reducing injury as follows:
There were five survivable accidents in which shoulder harnesses were worn by only one of two front‑seat occupants. A comparison was made of the relative injuries of each occupant. It was found in each case that injury severity was less for the occupant who wore the shoulder harness.
For example, in one accident each of two occupants sustained serious injuries, but the pilot, wearing a shoulder harness, sustained a broken leg and a slight concussion while the passenger without a shoulder harness sustained severe head injuries. The differences in the injuries in these comparisons were related to head and upper body injuries. Those persons who wore shoulder harnesses had markedly fewer head injuries.
The research also showed that if an aircraft occupant wore a shoulder harness, they increased their chances of survival by 20 per cent. Further, the chance of serious injury decreased by 32 per cent.
Liveable space
From photographs obtained of the wreckage, the occupied cabin area within the fuselage was compromised by the impact sequence. Figure 3 shows how the forward floor of the cabin under the instrument panel was crushed when the nose gear collapsed. The impact had buckled the floor under the seats, and the fuselage was breached behind the rear cabin bulkhead. The instrument panels had become dislodged and pushed rearward as a result of the nose impacting the ground. The cabin roof and wings had moved forward as a result of the nose section of the aircraft impacting the ground, reducing the cabin height. All of this damage reduced the survivable space within the cabin area.
Figure 3: Crush damage to accident aircraft compared to exemplar Cessna 150
Source: SA police modified by ATSB
Impact forces and pilot injury
A number of methods are available for measuring the impact forces an occupant is likely to experience during impact. While the outcome gives an appreciation of whether an accident is potentially survivable, the results should be interpreted with caution, as a number of variables do exist during an accident sequence. From the available data, the pilot would have sustained severe to fatal injuries as a result of the calculated impact forces.
The stall/spin condition
TheAerial Mustering Code of Practice[3] included a discussion on a specific stall/spin type of accident that had been observed in a number of low-level fatal accidents involving mustering operations. The common theme was a stall leading to the aircraft impacting terrain in a steep nose down pitch attitude. The sequence of events in these type of accidents followed a similar path to the accident aircraft.
Recovery from these stall/spin conditions required significant altitude. A figure of about 400 ft or more is often quoted. From an accident perspective, the strongest indication of a stall/spin is the steep nose down attitude, particularly when the aircraft was operating at low altitude. Without the spin entry, a Cessna stall typically will not drop the nose to a steep pitch down attitude.
Related/previous occurrences
The ATSB has investigated a number of accidents where a Cessna type aircraft have stalled and impacted terrain. Each of these accidents identify that, while the stalling characteristics of these aircraft types is benign, the stall condition is exacerbated through mishandling of the aircraft during the stall, which can result in entry into a spin. The stall/spin will result in a steep pitch down and rotation towards the stalled wing. Recovery from this condition will take a considerable amount of altitude, the magnitude of which is dependent on the speed of response by the pilot and the use of appropriate control inputs.
AO-2010-047: Cessna 172H, VH-RZV, Loss of control 30 June 2010, 21 km NNW of Cunnamulla, Queensland
While orbiting a water trough at about 500 ft, the pilot lost control of the aircraft. The aircraft impacted the ground and sustained serious damage.
The damage to RZV was consistent with the right-wing colliding with a tree branch followed by the aircraft impacting the ground inverted, with a steep nose-down attitude.
The pilot sustained serious injuries as a result of the impact and was unable to clearly recall the accident. The pilot reported that although he does not recall hearing the aircraft’s stall warning system, the most likely reason for the accident was an inadvertent stall. This probably occurred while the pilot was performing a steep turn with his attention divided between flying the aircraft and looking for cattle.
Investigation number 200506306: Cessna 150G, VH-KPQ, Loss of control 6 December 2005, 156 km north of Broken Hill, NSW.
At about 0835 Eastern Daylight-saving Time, the pilot was observed to circle some sheep at about 250 ft above ground level. Shortly after, ground mustering personnel noticed smoke nearby and found that the aircraft had impacted the ground and there was an intense fire. The pilot, who was the sole occupant of the aircraft, was fatally injured.
The aircraft wreckage was found approximately 400 m to the south-east from where the pilot was circling. The aircraft was upright with evidence of severe impact damage to the left wing, nose section and rear fuselage.
Examination of the aircraft, including the flight control systems and engine, did not reveal any evidence of pre-impact defects. Damage to the propeller indicated that the engine was operating at ground impact. The wing flaps observed in the retracted position.
The steepness of the angle of bank and the nose-down pitch attitude at the aircraft's point of ground impact indicated that the aircraft was in a steep left turn at that time. Those indications and the minimal forward movement of the aircraft after ground contact were consistent with the aircraft having stalled and slipped out of the turn. The lack of aircraft rotation at impact indicated that there had been insufficient time for the stall to develop into a spin, consistent with it occurring at low level.
The investigation concluded that the aircraft possibly stalled at a height from which the pilot was unable to recover.
This analysis will examine the operational factors surrounding the accident involving VH-RXU (RXU). Evidence from witnesses and inspection of the aircraft wreckage indicate that the pilot most likely lost control of the aircraft while executing a right turn. A lack of direct evidence needed to determine the aircrafts final stages of flight meant a reliance was placed on examining:
accident site observations
witness accounts
the operation of the aircraft, and
stall/spin characteristics of Cessna aircraft.
While there was no conclusive evidence that the pilot lost control of the aircraft by aerodynamically stalling during the right turn, the aircraft’s nose-down, and left-wing low attitude on impact could indicate a partial recovery following a stall or early stages of a spin (incipient spin). The pilot may have attempted to recover from this abnormal flight condition, however the aircraft’s altitude was insufficient, and the aircraft impacted terrain. The analysis will consider the circumstances that preceded the event.
Flight during cattle spotting operations
Aircraft handling
The mustering operations required aerial cattle spotting in support of stockmen mustering cattle. Unlike other mustering operations that relied upon aircraft flying at low level (below 500 ft) to herd cattle, aerial spotting did not require the pilot to fly that low. The primary use of the aircraft was to identify cattle and direct the ground-based stockmen to them. It was therefore likely that the pilot was flying at about 500 ft before the accident.
Witnesses reported that while spotting, the pilot conducted a series of turns or orbits overhead to locate the cattle and direct the stockmen to them by radio. Moments before the accident the aircraft was observed in a right turn. The stockman considered this a deliberate manoeuvre by the pilot to reposition the aircraft back toward the creek bed, behind the ground mustering crew.
To facilitate the turn, it was likely that the pilot applied flap and increased the aircraft’s angle of bank. The application of the observed 10 degrees flap selection would have allowed the pilot to fly the aircraft at a lower airspeed while maintaining a margin above the stall. However, the introduction of bank and/or unbalanced control inputs would have decreased the stall margin. Consequently, an adequate airspeed through appropriate power application during increased bank angles was essential to maintain the stall margin.
Distraction during manoeuvring
It was possible that during the turn the pilot’s primary focus was on manoeuvring the aircraft back toward the direction of the creek bed attempting to reacquire the cattle. Research has shown that when a pilot becomes distracted, the tendency for not monitoring the aircrafts energy state and/or adding unbalanced control inputs is increased. This has the potential to induce a stall or entry into a spin from low altitude. In this case, it could have led to the pilot losing control of the aircraft. A review of similar accident investigations highlighted that this was particularly evident when conducting turns during mustering operations or when conducting other tasks that require the pilots attention to ground based activities.
It has been highlighted in other accident investigation reports that Cessna considers that the height required to recover the aircraft from the stall/spin condition is significant, and at least in the order of 400 ft. It was therefore important that the pilot monitors and maintains an appropriate margin above the stall during a turn, be cautious with manoeuvring, and was balanced with control inputs when flying at lower altitudes.
While the degree of manoeuvre that led to the loss of control of the aircraft could not be determined, it was possible that in an attempt to reacquire the cattle, the pilot’s control inputs induced a stall leading to a possible incipient spin and collision with terrain. Had a stall/spin condition occurred or been imminent, the aircraft’s low impact angle may indicate a partial recovery, or is indicative of the early stages of a spin.
Seatbelt use while conducting in-flight manoeuvres
A number of studies and accident investigations have examined the use and effectiveness of various occupant restraints. The ability for the occupant to sustain less life-threatening injuries relied upon the use and appropriate fitment of the seatbelt or harness restraint. Lap/sash or full harness restraints are shown to reduce the incidence of flail type injuries during an accident.
Although in this case, the likelihood of the pilot sustaining flail related injuries would have reduced if the sash portion of the seatbelt restraint had been used, it could not be determined if it would have changed the outcome of the accident.
This accident highlights the importance of the appropriate use of restraints by pilots and passengers during all phases of flight. This is particularly the case during aircraft operations at low altitudes where little time exists to refit the restraint in the event of an abnormal inflight condition or emergency.
The use of unapproved fuel
It was reported by the operator that the fuel primarily used in VH-RXU was Avgas, sourced from an authorised refuelling facility in drums. However, the fuel sample taken from RXU after the accident was identified as a combination of Avgas and unleaded fuel (referred to as Mogas by the operator). This was consistent with the drum contents at Mosquito airfield.
Research has shown that using Mogas can have an effect on the formation of vapour lock in the fuel system, and carburettor icing. Despite this, the pilot successfully climbed the aircraft after refuelling from Mosquito airfield and recommenced spotting operations. There were no reported difficulties with aircraft performance.
It was considered that, despite the known issues with the use of Mogas, it was unlikely that in this case it resulted in poor engine performance or contributed to a loss of aircraft control.
Findings
From the evidence available, the following findings are made with respect to the loss of control and impact with terrain involving the Cessna Aircraft Company 150G, registered VH-RXU, that occurred 270 km SE Alice Springs, Northern Territory on 12 July 2016. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Contributing factors
While conducting a right turn at low altitude, the pilot lost control of the aircraft and was unable to recover before impacting terrain.
Other factors that increased risk
The pilot of the aircraft did not use the installed shoulder harness (sash), resulting in a greater risk of injury during the collision with terrain.
The use of unapproved fuels in aircraft increases the risk of engine performance related issues.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Pastoralists & Graziers Association (PGA) of WA (Inc), Aerial Mustering Code of Practice, West Perth, Western Australia. Cited in ATSB B2005/0055.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the aircraft operator, Civil Aviation Safety Authority and the South Australia police.
Submissions were received from the aircraft operator, Civil Aviation Safety Authority and the South Australia police. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 3 July 2016, a Cessna 150M aircraft, registered VH-TDZ (TDZ), and a Cessna 152 aircraft, registered VH-KTL (KTL), departed from the Exmouth aircraft landing area (ALA), Western Australia, to conduct whale shark spotting on the western side of the Exmouth peninsula. Each aircraft had only the pilot on board.
The east and west coasts of the Exmouth peninsula are separated by ranges with peaks of about 600 to 1,100 ft. The weather forecast for Learmonth Airport, located about 10 NM south of the Exmouth ALA,[1] included easterly winds and TEMPO[2] periods for reduced visibility and a cloud base of 800 ft. However, both aircraft were able to depart directly to the west from Exmouth ALA and track over the ranges in visual meteorological conditions (VMC).[3]
On the western side of the peninsula, they were joined by two other aircraft, also engaged in whale shark spotting. The four pilots set up vertical and horizontal separation between their aircraft for their whale shark spotting.
At about 1045 Western Standard Time (WST), the pilot of the aircraft operating to the north decided to return to Exmouth due to deteriorating weather approaching from the north. The other three pilots decided to continue whale shark spotting[4] and reported that the weather conditions improved temporarily after the first aircraft departed. However, about one hour later, the cloud base lowered and visibility reduced on the western side of the peninsula, and the three pilots collectively agreed to return to Exmouth.
As the deteriorating weather was approaching from the north, the pilots decided to track to the south and then east across the coastline and peninsula at an altitude of about 1,000 ft. As the aircraft flew eastward, the cloud base and visibility continued to lower. The pilot of TDZ assessed it was unsuitable to continue in that direction and the three aircraft turned around and headed west back to the coastline.
The first aircraft then returned to Exmouth ALA by flying over water around the north of the peninsula below the cloud base. The pilots of KTL and TDZ considered the weather conditions to the north to be unsuitable and therefore they decided to orbit overhead Yardie Creek Road (Figure 1) near the western coast of the peninsula to see if the weather conditions would improve. The pilot of KTL identified a straight section of the road, orientated north-south, as suitable for a precautionary landing. The pilot of TDZ also orbited over the road below the cloud base of about 500 ft.
While orbiting overhead the road, the pilots assessed the weather conditions to the north were continuing to deteriorate and unsuitable to attempt a return flight northward, either around the peninsula or to the Yardie homestead airstrip, located at the north-western end of the peninsula (Figure 1). After about 5–6 orbits, the pilot of KTL assessed that the weather was deteriorating, and after confirming that the road was clear of vehicles and other obstacles, conducted a landing on the road in a southerly direction. The pilot of KTL parked their aircraft at the southern end of the straight section of road and attempted to block the road while waiting for the pilot of TDZ to land.
The pilot of TDZ conducted three approaches to the road and performed go-arounds from the first two approaches due to vehicles on the road and the strength of the easterly wind. At about 1215, on their third approach, the pilot of TDZ landed the aircraft on the road. Both aircraft were subsequently moved clear of the road to allow vehicles to pass. The aircraft did not sustain any damage and the pilots were not injured.
Local police attended the scene and blocked the section of road when the pilots were ready to depart. The pilots inspected their aircraft, and after the weather conditions improved, they took off from the road and returned to Exmouth ALA.
Figure 1: Exmouth peninsula with key locations
Source: Google earth, annotated by ATSB
Visual Meteorological Conditions (VMC)
The whale shark spotting flights were local flights in Class G airspace in accordance with VMC procedures. This class of airspace required the following weather conditions when operating an aeroplane below 3,000 ft above mean sea level or below 1,000 ft above ground level, whichever was higher:
visibility of 5,000 m
clear of cloud and in sight of ground or water.
The pilots reported that at times when there is low cloud, which prevents them crossing the ranges in VMC, they fly coastal around the peninsula below the cloud base.
Weather forecast
The pilots’ flight planning included reviewing the Aerodrome Forecast (TAF)[5] for Learmonth Airport and the area forecast (ARFOR).[6] Learmonth was the closest airport to Exmouth ALA with a dedicated weather forecast service and the pilots used the TAF as an indication of local weather conditions for the eastern side of the peninsula. The pilots reported noting the TEMPO periods for reduced cloud base to 800 ft on the TAF (Figure 2).
The highlighted section of Figure 2 indicates the weather may deteriorate for periods between 30 and 60 minutes between 3 July 0800 WST and 4 July 0800 WST for visibility reduced to 3,000 m in rain with a broken[7] cloud base at 800 ft.
Figure 2: Learmonth TAF
Source: Bureau of Meteorology, annotated by ATSB
The ARFOR indicated rain and low cloud in the area with the possibility of heavy rain offshore. The minimum visibility forecast was 7 km in light rain, reducing to 1,000 m in heavy rain, and the minimum cloud base forecast was broken between 800 ft and 2,000 ft. The forecasted wind was easterly at the surface, but was between north-east and north-west from 1,000 to 10,000 ft.
Actual weather
At the time of their departure, the pilots noted that the cloud base was ‘well clear’ of the tops of the ranges, which permitted a VMC track to the west from Exmouth ALA. At about 1145, the pilots noted low cloud approaching from the north, which led to their decision to attempt to track south and east across the peninsula.
Figure 3 depicts the rainfall detected by the Learmonth weather radar at 1210, about the time that the pilots conducted their precautionary landing on the west coast.
The pilot of KTL reported that the cloud base was ‘about 300 ft’ and visibility was ‘about 4 km’, but reduced to ‘about 3 km to the north’ at the time of their precautionary landing. The pilot of TDZ, which landed after KTL, reported that the cloud base was ‘about 500 ft’ and visibility was ‘about 2‑3 NM’ at the time of their precautionary landing.
When the weather deteriorated, the pilots initially attempted to return to Exmouth by tracking across the southern end of the Exmouth peninsula. The deteriorating weather conditions were driven by the northerly winds, which meant that the northern end of the peninsula, including the Yardie homestead airstrip, would be affected by the low cloud and reduced visibility before it reached the southern end of the peninsula.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Operator of VH-TDZ
As a result of this occurrence, the aircraft operator of TDZ has advised the ATSB that they have taken the following safety action:
Operations manual amendment
The whale shark spotting section of the operations manual was amended to highlight the following:
Pilots are to use their judgement to make an early decision on deteriorating weather conditions. The Yardie Creek Homestead Caravan Park airstrip is to be used as the alternate landing site during periods of rain showers or low cloud and pilots are not to attempt to fly over the range in low cloud.
Operator of VH-KTL
As a result of this occurrence, the aircraft operator of KTL has advised the ATSB that they are taking the following safety action:
Operations manual amendment
Company pilots conducting aerial work operations are to maintain an awareness of meteorological conditions. In the event of deteriorating conditions due to cloud or rain, pilots will make an early decision and depart from the area that is potentially affected by loss of VMC. Pilots are to have an alternate plan in the event of deteriorating weather.
Safety message
This incident highlights the need for pilots to interpret the weather forecast within the context of their planned operation. In this case the ARFOR indicated low cloud, rain and visibility below VMC could approach their operating area from a northerly direction and affect the pilots’ poor‑weather exit strategy. Fortunately, during their attempt to cross the peninsula, the pilots had a return path to the coast open and were eventually able to safely land on a road and avoid entering instrument meteorological conditions.[8] There are several key factors for a VFR pilot to consider to avoid inadvertently entering IMC, which include:
thorough pre-flight planning
having alternate plans in the event of deteriorating weather
making timely decisions to turn back or divert.
An explanation of what the ARFOR message structure means for pilots is available from the Bureau of Meteorology’s Aviation Weather Products: Area Forecasts.
Further information about pre-flight planning considerations is available from the Civil Aviation Safety Authority’s Visual Flight Rules Guide.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 2 July 2016, at about 1420 Eastern Standard Time (EST), a de Havilland DH-82A aircraft, registered VH-ARU, departed Shute Harbour aircraft landing area (ALA), Queensland, for an aerobatic joy flight. On board were a pilot and one passenger.
When the aircraft reached about 4,500 ft over water, the pilot advised air traffic control (ATC) that they were commencing aerobatic operations. The pilot reported that they then raised the aircraft nose and reduced the throttle to idle. The aircraft then pitched nose-down and the pilot initiated a rotation to the left. After about one and a half rotations, the pilot levelled the aircraft wings and stopped the rotation. As the airspeed was then about 110 kt, which was the entry speed for the next manoeuvre (a loop), the pilot raised the aircraft nose and applied full power as the nose passed the horizon.
The aircraft was then passing about 3,500 to 4,000 ft on climb, when the pilot and passenger heard a bang. The pilot saw a small object fly past to their left in close proximity, and the passenger saw that the on-board camera had been knocked.
The pilot discontinued the manoeuvre and stabilised the aircraft in a glide attitude. As the aircraft continued to descend, the pilot elected to return to Shute Harbour ALA. The pilot reported that the aircraft was not vibrating and the tachometer was indicating maximum RPM. The pilot also assessed that the engine was not producing any thrust, regardless of the throttle position. The pilot advised ATC that they had completed operations and were returning to Shute Harbour. At no time did the pilot inform ATC that there was an emergency.
As the aircraft passed the highest terrain en route to Shute Harbour ALA, the pilot assessed that they were not going to be able to reach the ALA (Figure 1). The pilot then turned the aircraft to land on the beach at Funnel Bay, but sighted boats moored on the beach. The pilot therefore aimed to land the aircraft at Funnel Bay on the mudflats. The pilot conducted a forced landing onto the mud and the aircraft continued onto some rocks. After landing, as the pilot inspected the aircraft, they noticed that the propeller was missing.
Figure 1: Shute Harbour ALA and Funnel Bay
Source: Google earth – annotated by ATSB
The pilot was uninjured, and the passenger sustained minor injuries. The aircraft sustained substantial damage (Figure 2).
Figure 2: Accident site showing damage to VH-ARU
Source: Aircraft owner – modified by ATSB
Pilot comments
The pilot had completed a daily inspection of the aircraft earlier in the day and had subsequently flown it for about 6 minutes to assess the weather conditions. The incident flight was the first commercial flight of the day. During the pre-flight inspection, the pilot reported having made a visual check of the propeller for defects, gravel rash and any chips, but had not detected anything abnormal.
The pilot had asked the passenger their weight prior to the flight, and although they did not complete a weight and balance calculation, assessed that the aircraft was within its weight and balance limitations for aerobatic flight.
At the time of the incident, they were operating about 4 to 5 NM from the ALA, and over water. The pilot thought that the aircraft probably struck a bird resulting in the propeller failing.
When they realised that the aircraft was unable to reach the runway at Shute Harbour, the pilot had a secondary plan to land on the beach at Funnel Bay. They commented that their training helped to deal with the situation by being aware of their surroundings and having a series of plans in case of emergency.
Engineering report
The aircraft maintenance engineer assessed the aircraft after the incident and sent the remnants of the (timber) propeller that had remained attached to the aircraft to the ATSB. The engineer also spoke to the manufacturer of the propeller and was able to trace its history. The manufacturer suggested the propeller failure was indicative of a propeller overspeed, although they did not inspect the propeller remnants. The propeller was not retrieved as it failed when the aircraft was over water.
ATSB analysis
Video footage
The ATSB analysed the data card from the on-board camera. The camera was facing rearwards and no evidence of a birdstrike was visible on the footage when viewed frame-by-frame. Analysis of the sound component of the recording was conducted to determine the engine frequency at the time of the propeller failure, but the results were inconclusive due to background noise including a radio transmission.
From the video footage, it was evident that the aircraft entered a spiral manoeuvre that involved substantial rudder and aileron input such that the aircraft was in balance (not skidding or slipping sideways). The wings were then levelled and the aircraft pulled out of the dive. The propeller failed just as the aircraft nose passed back up through the horizon at the start of the next manoeuvre and power was applied. The propeller was under substantial load at this stage.
Propeller remnants
The ATSB examined two fragments of the propeller that were identified as parts of the hub section. An area of interest, depicted in Figure 3, showed evidence of bending consistent with the blade breaking away from the hub while under load. No bird remains were found on the fragments. The factors contributing to the propeller failure could not be determined from the timber fragments.
Figure 3: Propeller remnants
Source: ATSB analysis
ATSB comment
One of the findings of ATSB investigation AO-2013-226, In-flight break-up involving de Havilland DH82A Tiger Moth, VH-TSG, 300 m E of South Stradbroke Island, Queensland, 16 December 2013, was that ‘publicly-available video recordings showed that some Australian commercial Tiger Moth operators conducted aerobatic flick (otherwise known as ‘snap’) rolls and tailslide manoeuvres, which were prohibited by the Type Design Organisation’. However, the on-board video recording showed that the types of aerobatic manoeuvres conducted during the accident flight were all permitted for the aircraft type.
The ATSB cautions commercial vintage aircraft operators about the risks associated with aircraft age and the importance of understanding the originally-intended use of the design before commencing their operations.
Safety message
This incident highlights the value of always having a consideration of landing areas available in case a forced landing is required. Alerting air traffic control as emergencies arise enables them to provide the necessary and appropriate assistance.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 4 July 2016, at about 0940 Eastern Standard Time (EST), a Piper PA31‑325 aircraft, registered VH-ETW (ETW), departed from Birdsville Airport, Queensland for a scenic flight to Lake Eyre, South Australia and refuelling at Marree. The pilot and four passengers were on board the charter flight.
On the return flight to Birdsville, at about 1410, the pilot broadcast on the common traffic advisory frequency (CTAF) indicating that they were about 30 NM south-west of Birdsville for a landing on runway 32. Later a pilot of a SAAB 340 aircraft also broadcast on the CTAF that they were about 15 NM east of Birdsville for a straight in approach, landing on runway 32, with a similar arrival time to ETW.
The pilot of ETW overflew the airport at about 2,500 ft on the upwind end of runway 32 to reduce the possibility of a conflict with the arriving SAAB (Figure 1). ETW joined for a wide downwind leg of the circuit and the pilot lowered the landing gear. The pilot observed that the SAAB that had now landed had not vacated the runway, so the pilot retracted the landing gear and extended the downwind leg to allow further time for the SAAB to vacate the runway.
Figure 1: Birdsville airport showing the location of runway 32, the parking apron and where the birds (hawks) were generally located off the end of runway 32 (orange circle).
Source: Google earth, modified by the ATSB
The pilot conducted the downwind checklist that included checking that the landing gear was down and locked, however, as the landing gear was in the up position, this part of the checklist was not conducted. When the aircraft was towards the end of the downwind leg, the pilot selected the landing gear handle down. The pilot noticed that the landing gear selector moved out more easily than normal, but the pilot identified that three landing gear down green lights were illuminated, indicating that the landing gear was down and locked.
While the pilot was scanning out the window, they noticed a flicker of the instrument lights. When they looked back inside the cockpit, they observed that the GPS had gone back into initialising mode, which indicated that it may have lost power. During the turn onto the base leg of the circuit, the pilot gave a broadcast on the CTAF and conducted the base leg checklist items (they did not include checking the landing gear). The pilot noticed that the SAAB had not vacated the runway, but was getting close to exiting onto the apron. As the aircraft completed the turn onto the base leg, the pilot felt something against their right knee. The pilot reached down and found that it was the landing gear selector handle, which had become partially detached from the selector lever (Figure 2). The pilot took hold of the handle to ensure it was not lost and confirmed that there were three green landing gear down lights illuminated.
The pilot inserted the handle back into the landing gear selector lever and retracted and extended the landing gear to ensure that everything was operating correctly. The pilot removed the handle and kept hold of it and then gave a final leg broadcast, turned onto the final leg and conducted the finals checklist items. This checklist included a landing gear check, but the pilot could not remember clearly if there were three green lights.
At about 200 ft on final approach, the pilot observed a significant number of birds (hawks) (see orange circle in Figure 1). Due to a 15kt crosswind, as the pilot flared the aircraft for landing, the aircraft moved to the right side of the runway and the pilot then noticed that the aircraft had a slightly higher nose attitude than normal. As the attitude kept increasing, the pilot slowly advanced the throttles, then the rear footstep touched the runway and made a scraping noise. The pilot decided not to close the throttles as the aircraft was not on the runway centreline and they continued to advance the throttles. As the speed increased, the aircraft attitude adjusted and the propellers struck the runway. The aircraft speed had increased to take off speed and the pilot assessed that the safest option was to continue with a take-off. The pilot did not notice any abnormalities with the engines.
The pilot conducted a circuit, selected and held the landing gear handle in the down position and the aircraft landed without further incident. The pilot and passengers were uninjured and the aircraft had minor damage to the propellers (Figure 3).
Figure 3: Damage to ETW propellers
Source: Pilot, modified by the ATSB
Pilot comment
The pilot reported that when the landing gear was selected down when on the final approach, the landing gear selector was easier than usual to pull out and move past the neutral stop to the gear down position.
The pilot reported hearing a continuous horn sounding while in the landing flare just as the throttle was advanced and believed that it was the stall warning horn. The pilot believed that the landing gear horn would not have sounded as the throttles were not decreased past the location of the limit switches, which is where the throttles are almost closed (see Landing gear system below).
The pilot indicated that after parking the aircraft on the apron, when the avionic switch was moved to the off position, the avionics remained on and it was not until the switch had been cycled several times between the on and off position did the avionics turn off.
The pilot returned to the aircraft a few days later and noted that when the electrical master switch was turned on there were no green landing gear indicator lights despite the wheels being down, indicating the aircraft still had an avionics defect.
The pilot indicated that a maintenance release inspection (the periodic (100 hourly or 12-month) maintenance inspection) had been completed on 13 May 2016 and about 15 hours prior to the occurrence. The pilot had been the only pilot to fly the aircraft since the 100 hourly inspection and had flown a flight earlier that day and not noticed any issues with the aircraft.
Landing gear system
The landing gear handle is attached to the landing gear lever by a sleeve that fits over the end of the lever and is held in place by a pin, which is retained by a split pin. In this incident, the pin and split pin had fallen out of the landing gear handle and lever. In addition to connecting the handle to the lever, the pin also interacts with a gear handle stop (Figure 4). The landing gear handle is designed so the handle is spring-loaded to a forward position (towards the instrument panel). The pin on the inboard side of the handle rests against the gear handle stop for the neutral up and neutral down position. This ensures that the landing gear handle cannot unintentionally be moved beyond the neutral stop.
To select the landing gear down, the gear handle is pulled away from the instrument panel, down and over the gear handle stop to the full down position. When the landing gear is fully extended and locked, the landing gear handle will then return automatically to the down-neutral position where it is held by the pin against the gear handle stop.
Located on the instrument panel, above and to the right of the landing gear handle are one red and three green indicator lights (Figure 4). The red light will illuminate when the gear is not locked and the gear handle is either in the up or down position. When each of the individual gear is down and locked the respective green light will illuminate. There is no indication light when the gear is up and locked. When power from either engine is reduced below 10 to 12 inches of manifold pressure, a horn in the cockpit should sound if the gear is not down and locked.
Figure 4: Landing gear selector handle showing the gear handle, lever assembly, gear handle pin and the up and down neutral positions. In addition, the red unlocked light and the green down locked lights.
Source: Canada Transport Safety Board, modified by the ATSB
Operator report
The operator conducted an investigation into the occurrence and determined that the aircraft’s avionics were found to start up with the battery master switch, even though the avionics master switch was selected off. In addition, although the landing gear was down and locked, there were no green lights to indicate that this was the case. There was no indication of what the mechanical fault was in this system.
An inspection of the aircraft determined that when the gear handle was moved to the landing gear down position, it would normally return to the down neutral position. However, on the occurrence flight, the gear handle pin fell out. Without the gear handle pin to stop the landing gear lever at the gear handle stop, the lever continued to the gear up position (past the down neutral position to the up position) The landing gear retracted without the pilot being aware. However, the gear down and locked lights should have still illuminated prior to landing if the landing gear was down and locked.
Distractions for the pilot included the landing gear handle becoming detached, an issue with the avionics on downwind, numerous birds (kite hawks) that were flying around on final and the 15 kt crosswind.
Safety analysis
When the pilot had discovered that the landing gear selector handle had become detached, they used the detached handle to move the lever to retract and extend the landing gear to determine that there were no issues with the landing gear prior to the landing. The pilot then removed the handle to ensure that it did not fall and become inaccessible in flight, just in case the landing gear needed to be retracted and extended again. They believed that there were three green landing gear down indicator lights but was unaware that with the stop pin missing, the landing gear would self-retract after the landing gear handle was released. As a result, the pilot was not aware that the landing gear had retracted prior to landing.
There were a number of interruptions and distractions during the approach and landing phase of the flight. These included waiting for another aircraft to vacate the runway and subsequent alteration of the circuit to accommodate separation, issues with the GPS, the landing gear handle becoming free, large birds under the final approach and the crosswind during the landing. The combination of these interruptions, distractions and abnormal conditions likely contributed to the pilot flaring the aircraft for landing without realising the landing gear was in the retracted position.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The landing gear selector handle became detached and the landing gear retracting without the pilot’s knowledge.
Numerous distractions existed during the approach and landing that may have contributed to distract the pilot resulting in the aircraft landing with the landing gear in the retracted position.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Aircraft operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:
The pilot has undertaken comprehensive successful flight checks.
Aircraft defect rectification to ensure the aircraft is serviceable before further flight.
The aircraft operations manual will be amended to include actions to be taken when experiencing any abnormality with the aircraft’s landing gear. This will refer to the emergency procedures checklist and the aircraft flight manual. The procedure will require the pilot to:
abort the landing
climb to 1,500 ft
redo the pre-landing landing checklist to confirm green lights are on/or use the emergency landing gear hand pump to lower the landing gear.
conduct a visual inspection of landing gear to ensure it is down and locked.
All pilots will be informed of the incident via email or a safety alert to inform them:
of the importance of the gear control handle locking mechanism
to inspect the gear control handle on a regular basis for faults or damage
to look at additional options for confirming that the landing gear is down with the use of active control towers or having contact details of ground crew readily available to inspect the landing gear during a fly over.
Safety message
In the flying environment, interruptions and distractions can be subtle and brief and can interrupt the normal flow in the cockpit resulting in a preoccupation and distraction with one task to the detriment of another task.
The Flight Safety Foundation Approach and Landing Accident Reduction (ALAR) briefing note ‑ 2.4 - interruptions/distractions discuss that interruptions/ distractions may be subtle or brief where even a minor equipment malfunction can turn a routine flight into a challenging event. The primary effects of interruptions/distractions is to break the flow pattern of ongoing cockpit activities such as normal checklists and problem-solving activities. The briefing contains guidance that may assist in managing interruptions/ distractions.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
The ATSB has completed examination of the JRA-445-1 wing attachment fitting supplied by the Civil Aviation Safety Authority (CASA). In addition, an original Cessna wing attachment fitting (part no. 0811350-10), also supplied by CASA, was examined for comparison of the material properties and manufacturing methodology. A report detailing the examinations and findings was prepared and provided to CASA on 28 September 2016.
For further information regarding the wing fittings or airworthiness bulletin AWB 57-015, please contact CASA on 131 757 or www.casa.gov.au.
Updated: 30 June 2016
During an inspection of the wing attachment fittings of a Cessna 402C in accordance with Civil Aviation Safety Authority (CASA) airworthiness directive AD/CESSNA 400/92, a crack was identified in the inboard lower attachment fitting (Figure 1). The cracked attachment fitting (part number JRA‑445‑1) was manufactured by J&R Aerospace as a replacement for the original Cessna fitting.
Figure 1: Cessna 402C lower inboard wing main spar attachment fitting showing an approximate 100 mm (4 inch) crack (indicated by orange arrow) Source: CASA, annotated by ATSB
AD/CESSNA 400/92 specified inspection of the outboard attachment fittings, but not the inboard fittings. Compliance with the airworthiness directive was required prior to the component exceeding 5,000 hours time in service. The cracked JRA‑445‑1 fitting had accumulated 2,831 flight hours time in service.
On 17 June 2016, CASA issued airworthiness bulletin AWB 57‑015 to alert operators and maintainers of Cessna 400 series aircraft of premature cracking in a Cessna 402C wing attachment fitting manufactured by J&R Aerospace.
As part of their investigation, CASA requested the technical assistance of the Australian Transport Safety Bureau (ATSB) to conduct a metallurgical examination of the cracked fitting.To facilitate this assistance, the ATSB initiated an external investigation under the provisions of the Transport Safety Investigation Act 2003.
On 20 June 2016, a captain and first officer, employed by Cobham Aviation Services, conducted a QantasLink flight from Sydney Airport, New South Wales, to Canberra Airport, Australian Capital Territory, in a Boeing 717-200 aircraft, registered VH-YQV.
The aircraft arrived in Canberra at about 0720 Eastern Standard Time (EST), and the first officer then conducted an external inspection of the aircraft, while the captain prepared the cockpit including the take-off data for the next sector to Sydney. The captain wrote the reduced-thrust take-off data onto the take-off and landing data (TOLD) card, including a flex temperature[1] of 40 °C, which was obtained from a table in the regulated take-off (RTO) book, an engine pressure ratio (EPR)[2] of 1.39, aircraft take-off weight, flap setting 5, and the take-off reference speeds (V speeds).[3] As the runway was wet, the V speeds were obtained manually from a table in the RTO book.[4]
After completing the external inspection, the first officer returned to the cockpit and the flight crew checked the take-off data in accordance with standard procedures. The first officer assessed that based on the environmental conditions, the flex temperature should be 39°. The first officer amended the TOLD card by striking through the 40 and writing 39 next to it, and similarly amended the V speeds based on the manual V speeds provided in the table for that flex temperature.
The captain was the pilot flying[5] for the sector to Sydney, so commenced briefing for the flight. The captain read out the data from the TOLD card, including the flex temperature and EPR, and the first officer entered the flex temperature and V speeds into the take-off page of the flight management system (FMS), which then calculated an EPR.
The flight crew then completed the cockpit checklist down to the last four items, in accordance with standard procedures. At that time, a member of the cabin crew entered the cockpit to advise the flight crew that an additional 22 passengers would be boarding the flight. As the aircraft take-off weight would increase by about 2 tonnes, the first officer recalculated the take-off data. The newly derived flex temperature was 34°, and as there was not much room left on the TOLD card, the first officer overwrote the previous figure of 39 with 34. The first officer then obtained the new V speeds, which the captain crosschecked and the first officer wrote them on the TOLD card.
The aircraft communications, addressing and reporting system (ACARS) then chimed with the loadsheet coming through on the printer, and at about the same time, a cabin crewmember entered the cockpit to confirm passenger numbers and ground personnel communicated over the intercom with the flight crew about removing the wheel chocks. After entering the zero fuel weight from the loadsheet into the FMS and crosschecking the take-off weight in the FMS against the take-off weight derived on the TOLD card, the captain called for the first officer to enter the revised manually derived V speeds from the TOLD card into the FMS.
The standard procedure then was for the captain to call ‘re-flex’ before entering the amended flex temperature and flap setting from the TOLD card into the FMS. The captain was holding the TOLD card and reported stating ‘39’ as the flex temperature, having misread the ‘34’. The first officer could not recall checking the flex temperature in the FMS at that time, and thought it may have been omitted due to the interruptions.
The crew reported that the EPR calculated by the FMS based on the flex temperature and environmental conditions was 1.39. (The flight data showed that the commanded EPR at that stage was actually 1.38.) The EPR obtained from the RTO book (for flex temperature of 34°) and written on the TOLD card was 1.41. The flight crew crosschecked the FMS EPR with the TOLD card EPR, and although there was a discrepancy of 0.2, it was within the 0.3 margin allowed at that stage.[6]
After obtaining the required air traffic control clearances, the captain taxied the aircraft to the runway and commenced the take-off at about 0812. In accordance with standard procedures, the captain then moved the thrust levers forward and checked for an even spool-up of the engines to an EPR of 1.2. The captain then called ‘auto flight’ and the first officer engaged the auto-flight system. This action caused the thrust levers to move to a position where the EPR from the FMS was achieved. The captain then called ‘check thrust’ and the first officer saw that the EPR was 1.38, instead of the required EPR of 1.41 as written on the TOLD card. In accordance with standard procedures, the first officer then moved the thrust levers forward to achieve 1.41 EPR.
The flight crew thought that the aircraft was then correctly configured for the take-off, with the correct EPR, thrust and flap settings and V speeds, and the captain continued the flight. However, after about 4 seconds at 1.41, the EPR returned to 1.38 for the take-off as the thrust lever position returned to that set by the auto-flight system based on the EPR value in the FMS.
During the initial climb, the first officer identified that the flex temperature set in the FMS was 39 instead of 34. As the short sector to Sydney was busy, the crew waited until the aircraft had arrived in Sydney before discussing the incident. Both members of the flight crew assessed that tiredness due to the early start may have contributed to the flex temperature error, but that they were fit to continue to operate for the remainder of the day’s duty.
Flight data
The aircraft operator provided the ATSB with a copy of the quick access recorder (QAR) data for the incident flight. As depicted in Figure 1, the data showed the thrust lever angle set at about 25° and the EPR at 1.38 early in the take-off run. After about 4 seconds at that setting, the thrust lever angle increased to about 26° as the commanded EPR, followed closely by the actual EPR, increased to 1.41. However, after about 4 seconds at 1.41 and a further 6 seconds at 1.39, the EPR reduced to 1.38 and thrust lever angle to about 25°, where they remained for the take-off.
This indicates that although the first officer manually moved the thrust levers forward, as the auto-throttle system was engaged, it then overrode the manual thrust lever position and returned the EPR to the value set in the FMS, which was the target thrust setting. At the time, the computed airspeed was 54 kt. When the airspeed reaches 80 kt in the take-off roll, the auto-throttle system mode changes from ‘take-off thrust’ to ‘take-off clamp’ mode. In clamp mode, the auto-throttle servo does not have power and the thrust levers do not move automatically. However, in take-off thrust mode (prior to 80 kt), the flight crew would have to disengage the auto-throttle system to set the thrust manually, or maintain pressure on the levers until the airspeed reached 80 kt.
Figure 1: Graph of flight data from the incident flight
Source: QAR data supplied by the aircraft operator analysed by the ATSB
Flight crew comments
During the approach into Canberra from Sydney, the cloud base was at the minima.[7] The captain commented that the workload on an instrument approach down to the minima was high, and would generally result in a reduced state of arousal after landing and shutdown in response.
The flight crew commented that a combination of distraction by cabin crew and ground personnel while re-entering data, a reduced state of arousal following high workload instrument approach, and possibly tiredness from an early start may have contributed to their omitting to enter the correct flex temperature into the FMS.
Although the captain recalled misreading 39 instead of 34, the first officer could not recall the captain calling ‘re-flex’, and commented that it was unlikely to have been called and then not completed. The first officer thought it was more likely that they entered the new V speeds but had omitted to check that the flex temperature written on the TOLD card matched that in the FMS.
Normally by the time they are getting to the third set of amended numbers, the first officer would start a new TOLD card. However, as it was approaching the scheduled departure time, the first officer elected to overwrite the existing figures. The captain further commented that in future, if there were any more than two corrections made to the supplement data on the TOLD card, they would write out a new card.
The captain commented that this incident provided a good example of how adherence to standard operating procedures helps to mitigate errors. While the initial crosscheck prior to taxiing showed a discrepancy between the TOLD card and FMS EPR values, as it was within the permitted tolerance, the flex temperature error was not identified at that time. When the first officer checked the thrust (and EPR) during the take-off run, the too-low EPR setting was identified and the thrust levers set to obtain the correct EPR. Hence following the standard operating procedures provided sufficient risk control to identify and correct the error.
Tiredness
The flight crew signed on at 0505 for a four-sector flight duty from Sydney. The scheduled departure time for their first flight from Sydney was 0620 and the flight crew were required to sign on 1 hour and 15 minutes prior. In addition, the crew had to allow 30 minutes to transfer from the long-term carpark, pass through airport security, and sign on in the crew room in the domestic terminal at Sydney Airport.
The captain reported waking up at 0340 and the first officer at 0305, and both crewmembers reported conducting a self-assessment of their fitness to fly. The first officer reported feeling ‘somewhat tired’ having had a broken night’s sleep, but had the previous four days off work and did not feel fatigued. The captain also reported feeling tired having woken up early, they assessed they were not fatigued, and were fully fit to fly. Both the captain and first officer commented that the early start times generally caused a feeling of tiredness, but did not affect their ability to operate the aircraft.
Cobham operates flight and duty time limitations based on Civil Aviation Order 48 and an exemption, and had not, nor was required to have, implemented a fatigue risk management system. The flight crew reported that the company operations manual included a statement that it is the flight crew’s responsibility to determine their fitness to fly.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following safety action in response to this occurrence.
Aircraft operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:
Communication to flight crew
The operator will remind pilots to use a new TOLD card in the event that the card data is being changed and comprehension of these changes is not clear. Pilots will be advised of the investigation by its inclusion in the company’s staff safety magazine.
Safety message
Inaccurate take‑off reference data has potentially serious consequences. ATSB Aviation Research and Analysis Report AR-2009-052 (Take-off performance calculation and entry errors: A global perspective) documents a number of accidents and incidents where take‑off performance data was inaccurate. The report analyses those accidents and incidents, and concludes:
… it is imperative that the aviation industry continues to explore solutions to firstly minimise the opportunities for take‑off performance parameter errors from occurring and secondly, maximise the chance that any errors that do occur are detected and/or do not lead to negative consequences.
The ATSB SafetyWatch highlights the broad safety concerns that come out of our investigation findings and from the occurrence data reported to us by industry. One of the safety concerns relates to data input errors.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
----------
[1] Flex temperature is a calculated outside temperature used for a reduced thrust take-off. The flex temperature (which is hotter than actual outside temperature) is used for generating take-off parameters rather than the actual outside temperature. It takes into account the runway length and aircraft weight to ensure the aircraft can take off within the runway distance available and maintain the required obstacle clearance during the subsequent climb. The aim is to prolong engine life.
[2] The engine pressure ratio, or EPR, is a pressure ratio indicative of engine thrust. The pressure is sensed by two probes, one ahead and one aft of the jet engine fan.
[3] Take-off reference speeds or V speeds assist pilots in determining when a rejected take-off can be initiated, and when the aircraft can rotate, lift-off and climb.
[4] For a dry runway, the V speeds used would have been automatically generated by the flight management system.
[5] Pilot flying (PF) and pilot monitoring (PM) are procedurally assigned roles with specifically assigned duties at specific stages of a flight. The PF does most of the flying, except in defined circumstances; such as planning for descent, approach and landing. The PM carries out support duties and monitors the PF’s actions and aircraft flight path.
[6] A change in bleed configuration, such as selecting air conditioning packs on or off, can change the EPR value. Therefore there is a small discrepancy allowed while parked and during taxi, but the two figures must match at take-off
[7] For a precision approach, the minima is defined as a decision altitude at which a missed approach must be initiated if the required visual reference to continue the approach has not been established.
On Monday 27 June 2016, the Indonesian National Transportation Safety Committee (NTSC) commenced an investigation into damage sustained by ATR 72 aircraft, registered PK-WGL. Initial examination of this damage suggested similarities with that found on an Australian-registered ATR 72, registered VH-FVR, which is being investigated by the ATSB (see ATSB investigation AO-2014-032 at ATSB website). On 29 June 2016, the NTSC requested the appointment of an ATSB accredited representative to the NTSC investigation in accordance with clause 5.23 of Annex 13 to the Convention on International Civil Aviation Aircraft Accident and Incident Investigation. This was a result of the ATSB’s experience with the ATR during investigation AO-2014-032 and an accredited representative was appointed to the NTSC investigation that day. To facilitate this support, the ATSB initiated an investigation under the Australian Transport Safety Investigation Act 2003.
The ATSB has completed their role in assisting the Indonesian NTSC.
The NTSC is responsible for, and will administer the release of the final investigation report into the occurrence involving PK-WGL. Any enquiries regarding the NTSC investigation should, in the first instance, be directed to the:
National Transportation Safety Committee Ministry Of Transportation Republic Of Indonesia Transportation Building 3rd Floor Jalan Medan Merdeka Timur No. 5 Jakarta Pusat 10110 Indonesia
On 21 June 2016, a Qantas Airways Boeing 747-438 aircraft, registered VH-OJS, operated flight QF11 from Los Angeles, California, United States to New York, New York, United States.
At about 0700 Coordinated Universal Time (UTC), a cabin crewmember responded to a request for assistance from a passenger seated in business class seat 3A. The passenger advised the crewmember of a missing personal electronic device (PED). The PED was identified as containing a lithium type battery. The crewmember, along with the passenger, searched around the seat for the missing PED. While searching, the seat position was moved. As the seat moved, the passenger in the next seat observed the PED within the seat mechanism. The seat was then inadvertently moved, resulting in the PED being crushed (Figure 1). The crushed PED immediately began hissing and emitting smoke. Moments later, the PED ignited. A second crewmember then initiated the basic fire drill.
The second crewmember obtained a fire extinguisher, and as they proceeded toward seat 3A, they advised a third crewmember of the incident and requested assistance. This crewmember also obtained a fire extinguisher and proceeded toward seat 3A. The customer service manager (CSM) and another crewmember observed the activity and also followed, providing additional support.
When the cabin crewmembers carrying fire extinguishers arrived at seat 3A, they observed an orange glow emanating from the seat. A crewmember discharged a fire extinguisher into the seat, extinguishing the glow. At this time, the CSM acted as a communicator with the flight crew to inform them and keep them updated on the incident.
After confirming the PED fire had been extinguished, the cabin crew attempted to remove the PED in order to place the device in water, in accordance with lithium type battery fire procedures. The PED could not be removed without further damage and risk of fire. Therefore, the cabin crew elected to leave the device in place and position a crewmember with a fire extinguisher near seat 3A for the remainder of the flight. About 10–15 minutes after the incident, this crewmember identified further heat coming from the crushed PED. They again discharged the fire extinguisher onto the PED, eliminating the heat.
After confirming the incident was contained, the CSM advised the captain that the situation was under control. The captain discussed the incident with the first officer and considered the event had been dealt with appropriately. The flight proceeded to New York and landed about 40 minutes later without further incident.
Two passengers reported feeling unwell after the event, but it was unclear if this was as a result of the incident. The aircraft seat sustained minor damage.
Figure 1: Crushed PED after removal from seat
Source: Qantas
Cabin crew comment
The responding cabin crewmember commented that the provision of designated storage close to the charging port could assist in preventing PEDs entering seat structure.
Passenger comment
The passenger in seat 3A commented that the amenities pack provided to passengers in this seat type could be changed to include PED storage. This could assist preventing PEDs entering the seat structure.
Operator investigation report
The aircraft operator investigated the incident and provided a copy of their investigation report to the ATSB. The report included the following:
A review of reported events revealed 22 similar occurrences of trapped or crushed PEDs. Seven of these occurrences resulted in smoke and/or heat being produced. This incident was the first event to result in fire.
The investigation determined that the likely area for the PED to intrude into the seat mechanism was adjacent to the seat belt anchor point. This area becomes more exposed as the seat reclines towards the flat position.
Mesh netting within the seat structure is designed to capture objects that fall behind the seat. Damage to seat 3A consisted of an approximate 5 cm melt area to this mesh netting. There was no other damage noted to the seat structure.
Lithium batteries are capable of ignition and subsequent explosion due to overheating. Overheating may be caused by shorting, rapid discharge or overcharging. Overheating results in thermal runaway, which is a chemical reaction within the battery causing the internal temperature and pressure to rise. The result is the release of flammable electrolyte from the battery and, in the case of disposable lithium batteries, the release of molten burning lithium. Once one battery cell goes into thermal runaway, it produces enough heat to cause adjacent battery cells to also go into thermal runaway. This produces a fire that repeatedly flares up as each battery cell in turn ruptures and releases its contents.
SAFO 09013 Supplement also details the following information on fighting fires caused by lithium type batteries:
Relocate passengers away from the device.
Utilise a halon, halon replacement, or water fire extinguisher to prevent the spread of the fire to adjacent battery cells and materials.
Pour water, or other non-alcoholic liquid, from any available source over the cells immediately after knockdown or extinguishment of the fire.
Only water or other non-alcoholic liquid can provide sufficient cooling to prevent re-ignition and/or propagation of the fire to adjacent batteries. Water, though it may react with the tiny amount of lithium metal found in a disposable battery, is most effective at cooling remaining cells, stopping thermal runaway and preventing additional flare-ups. Significant cooling is needed to prevent the spread of fire to additional cells in a battery pack.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Seat manufacturer
As a result of this occurrence, the aircraft operator has advised the ATSB that the seat manufacturer is developing design solutions to prevent ingress of PEDs into the seat structure.
Aircraft operator
The aircraft operator has advised the ATSB that they are taking the following safety actions:
Changes to passenger briefings
An enhanced passenger briefing has been released to include:
If you lose your electronic devices at any time, it’s important you don’t move your seat as this could severely damage your device and may be a fire hazard. Please contact a crew member who will be able to recover your device.
A cabin crew service brief has been released which includes:
Passenger announcement to remind passengers not to move seats when devices have been lost.
Individual interactions between cabin crew and passengers when preparing the bed to include a discussion to raise passenger awareness of the possibility that the PED could be crushed if it is lost during the flight.
Establishment of working group
A working group has been established to develop further solutions for this issue.
Safety message
This incident serves as an excellent example of an effective response to an emergency situation. The cabin crew quickly implemented the basic fire drill procedure. This defined the roles and responsibilities of the responding crew, enabling a rapid and coordinated response to the incident using all available resources. As a result, the incident was quickly and effectively contained. The effective implementation of this procedure also ensured the flight crew were kept informed as the situation developed.
This incident also highlights the hazards of transporting lithium-ion battery powered PEDs aboard aircraft. The Civil Aviation Safety Authority has released information on the safe carriage of lithium type battery powered devices aboard aircraft in the web page: Travelling safely with batteries and pamphlet: Is your luggage safe?
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Occurrence summary
Investigation number
AO-2016-066
Occurrence date
21/06/2016
Location
500 km WNW of John F. Kennedy International Airport, United States