Collision with terrain involving Lockheed Martin Stalker XE UAS, Avoca Race Track, Victoria, on 25 October 2016

Final report

Report release date: 09/02/2017

What happened

On 25 October 2016, an instructor was supervising students in the operation of a Lockheed Martin Stalker eXtended Endurance (XE) unmanned aerial system (UAS) (Figure 1) at the Avoca racetrack in Victoria.

Figure 1: Typical Stalker XE aircraft

Figure 1: Typical Stalker XE aircraft

Source: UAS manufacturer

At about 1700 Eastern Daylight-saving Time (EDT), the instructor reviewed the student’s programmed mission and proceeded through the ground control station (GCS) launch wizard application. The launch wizard functions as a pre-flight checklist and ensures that all systems are ready for flight and that the mission is valid. The student then armed the aircraft for launch, pulled the aircraft back on the bungee cord and released the aircraft in accordance with the normal bungee launch procedures.

After release, the aircraft tracked straight ahead for 10 seconds according to standard operation, then climbed and commenced a right turn towards the first programmed waypoint. After passing the first waypoint, the aircraft made another right turn towards the second waypoint. About 20 seconds into the flight, the aircraft entered an uncontrolled descent from about 225 ft above ground level and collided with the ground. The aircraft sustained substantial damage, and no one was injured.

Manufacturer’s investigation

Power failure

The aircraft was powered by a lithium polymer battery. A battery adapter cable was plugged into the aircraft’s battery. The adapter cable was connected to the aircraft’s main power cable via the main power (battery) connector. The main power cable was secured into a pocket at the back of the connector pin.

After the accident, the aircraft’s negative main power cable was found to have separated from its pin in the connector.

The battery connector consisted of two mating pairs of contacts. In normal operation, all current flow passed through spring contacts on the male plug to the female contact. Spring tension increased the mating area and generated pressure upon the surfaces.

A different Stalker XE aircraft also experienced a battery connector failure about one month prior to this incident. In both incidents, the failed battery connector pins had the following problems:

  • significant pitting and erosion of the outer quarter of the male contact
  • heat damage to the spring contact surface
  • loss of spring tension in most or all of the contact springs
  • minor pitting of the outermost edge of the female contact.

It was determined that the capacitive load of the electrical system caused inrush current,[1] and the operator payload and communication links increased both the capacitive load and the power draw. The contact damage from the inrush current initiated the failure process. Sustained current, which produced contact heating, then removed the contact temper[2] and significantly degraded the connection. The manufacturer was able to duplicate the unsoldering failures via this mechanism.

The connector failure was likely the result of multiple factors:

  • Inrush current produced pitting, erosion and metal splatter on other contact surfaces.
  • The erosion and splatter then produced localised areas of very high current density.
  • The current density resulted in localised hotspots that removed the spring contact temper, which produced very high resistance on that spring contact.
  • The load was then distributed across the remaining spring contacts, compounding the failure rate.
  • Eventually the connector resistance was high enough that the normal operating current heated the solder joint until the solder melted and the circuit was interrupted.

The first steps probably took many flight cycles to develop, while the last probably required only seconds to a few minutes of normal operating current.

The separation of the negative main power cable from its pin in the main power connector interrupted electrical power to all of the aircraft systems. This included the autopilot, motor and control surface servos.

Uncontrolled flight

The flight data stopped suddenly at 225 ft – the subsequent lack of data logging indicated a power interruption to the autopilot.

Once battery power was lost, all systems in the aircraft were inoperative and any subsequent ‘flight’ was uncontrolled. Due to the loss of electrical power to the motor and the autopilot, the aircraft was unable to glide to a safe landing.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The main power connector pins had sustained degradation from arcing and high temperatures due to inrush current, resulting in increased resistance.
  • During the initial climb, high current across the increased resistance of the main power connector heated the negative pin to a temperature high enough to melt the solder on the negative main power cable.
  • The separation of the negative main power cable from its pin in the main power connector interrupted electrical power to all aircraft systems, including the autopilot, motor and control surface servos.
  • Due to the total loss of electrical power, the aircraft was unable to maintain normal flight or conduct a safe glide landing, therefore collided with the ground.

Safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following safety action in response to this occurrence.

Aircraft manufacturer

As a result of this occurrence, the aircraft manufacturer has advised the ATSB that they are taking the following safety actions with regard to Stalker XE aircraft:

  • All battery connectors are being replaced and sacrificial pigtails are being added to the connectors, to be replaced after a number of connections.
  • The aircraft battery circuitry is being modified to prevent arcing during connection and disconnection.

Aviation Short Investigations Bulletin - Issue 57

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

__________

  1. Inrush current, input surge current or switch-on surge is the maximum, instantaneous input current drawn by an electrical device when first turned on (Wikipedia).
  2. Tempering involves heating steel to a specific temperature to achieve certain properties such as hardness and elasticity and to remove brittleness.

Occurrence summary

Investigation number AO-2016-141
Occurrence date 25/10/2016
Location Avoca Race Track
State Victoria
Report release date 09/02/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Lockheed Martin Skunk Works
Model Stalker XE
Sector Remotely piloted aircraft
Operation type Aerial Work
Departure point Near Maryborough, Victoria
Destination Near Maryborough, Victoria
Damage Destroyed

Collision with terrain - Beech Aircraft Corp 58, VH-HSZ, Geraldton, Western Australia, on 25 August 1992

Summary

The aircraft departed Denham for travel to Perth via a refuelling stop at Geraldton.

At about 0806 hours the aircraft crashed approximately 770 metres, bearing 347°M from the threshold of runway 21 at Geraldton, apparently out of control and with the stall warning audible throughout the final radio transmission.

Investigation Indicated that both engines had stopped prior to Impact due to fuel exhaustion. There were no Indications of fuel leaks, and an analysis of times flown by the aircraft preceding the crash revealed that the available fuel should have been exhausted at about the time the engines were reported to have stopped. Fuel was available at Denham but, for unknown reasons, was not utilised by the pilot.

The pilot did not lodge a flight plan with the Civil Aviation Authority nor was any evidence found in the wreckage to Indicate that the pilot had used a flight plan or fuel log enroute. No conclusive determination for the loss of control of the aircraft was reached, however, the proximity to the threshold of runway 21 and the configuration of the aircraft with the wheels down, suggests that the pilot may have been attempting to turn towards that runway for a glide approach and landing.

SIGNIFICANT FACTORS

The following factors were considered relevant to the development of the accident:

1. The aircraft departed Denham with Insufficient fuel for the flight to Geraldton.
2. The pilot was apparently unaware that the fuel state was Inadequate and did not refuel at Denham.
3. Both engines stopped due to fuel exhaustion.
4. Control of the aircraft was lost at a height which did not allow the pilot to recover.

Occurrence summary

Investigation number 199200230
Occurrence date 25/08/1992
Location Geraldton
State Western Australia
Report release date 05/03/1993
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain, Fuel exhaustion
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Beech Aircraft Corp
Model 58
Registration VH-HSZ
Serial number TH777
Sector Piston
Operation type Private
Departure point Denham, WA
Destination Geraldton, WA
Damage Destroyed

Near collision involving Pilatus BN2, VH-IOA, and Bombardier DHC-8, VH-ZZJ, Horn Island Airport, Queensland, on 12 October 2016

Final report

Report release date: 09/02/2017

What happened

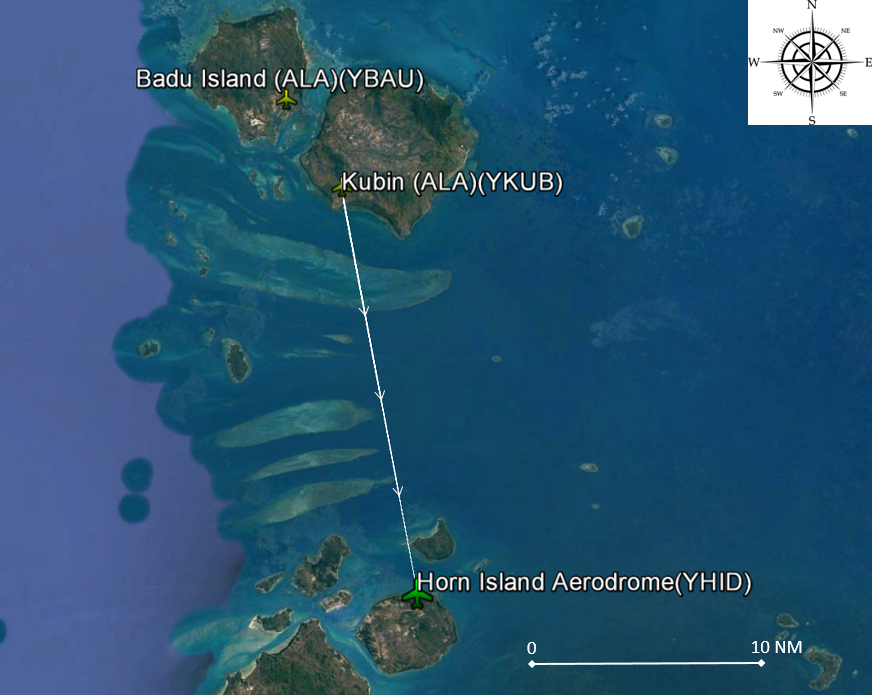
On 12 October 2016, at about 1330 Eastern Standard Time (EST), a Pilatus BN2A-20, registered VH-IOA (IOA), departed from Kubin on a charter flight to Horn Island, Queensland (Figure 1). On board IOA were one pilot and two passengers. At about the same time, a Bombardier DHC-8-202, registered VH-ZZJ (ZZJ), conducting surveillance operations, was preparing for departure from Horn Island. On board ZZJ were two pilots and three crewmembers.

Figure 1: IOA track from Kubin to Horn Island

Figure 1: IOA track from Kubin to Horn Island

Source: Google earth, annotated by ATSB

The Kubin authorised landing area (ALA) is within the Horn Island broadcast zone, and the pilot of IOA reported that they made their departure call on the Horn Island common traffic advisory frequency (CTAF). At the time IOA departed from Kubin, a faster company aircraft, registered VH-WOT (WOT), departed from Badu Island (Figure 1) on track to Horn Island. In addition to WOT, there was a training aircraft conducting circuits on runway 08 at Horn Island. While tracking to Horn Island, the pilot flying IOA heard a radio broadcast from WOT, which indicated they would join the runway 08 circuit as number 2 to the training aircraft. The area controller[1] then passed IOA traffic information about a DHC-8 (ZZJ) aircraft taxiing at Horn Island for departure from runway 08. The pilot flying IOA planned to join a straight-in approach to runway 14 from their track from Kubin. The pilot reported that they made all the required radio broadcasts for an arrival to Horn Island including broadcasts at 10 NM, 5 NM and 3 NM before they joined the final approach for runway 14.

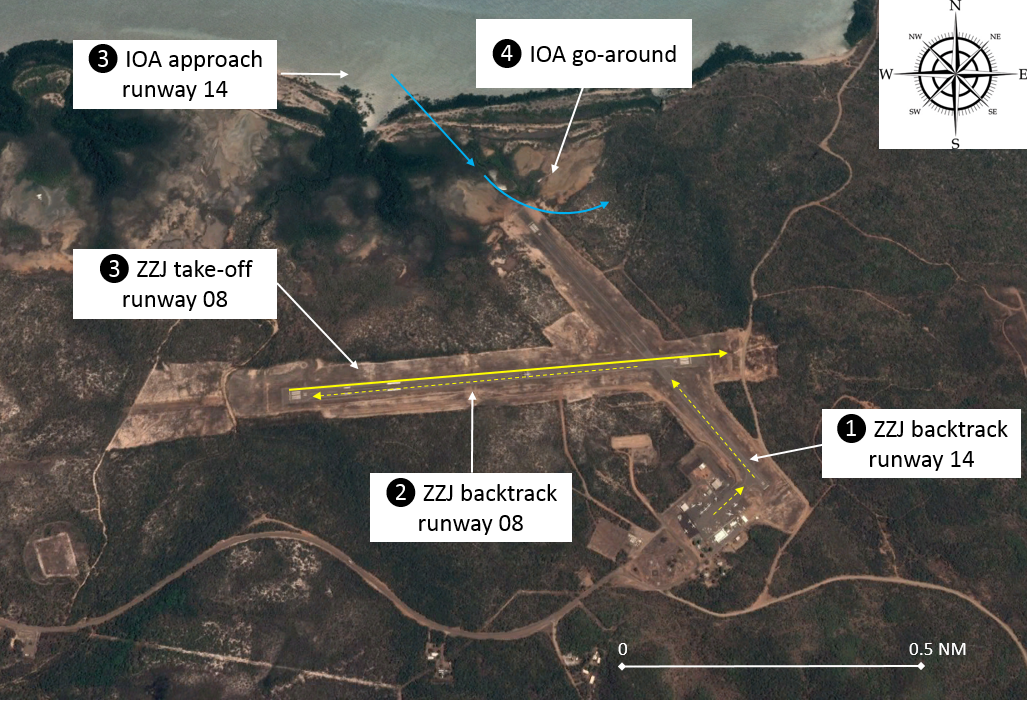
The first officer on board ZZJ made a broadcast they were entering and backtracking runway 14 at Horn Island for a departure from runway 08 (position 1 on Figure 2). Just prior to the intersection of the two runways, ZZJ held short of runway 08 to allow the training aircraft to complete a touch-and-go landing on runway 08. The first officer then broadcast ZZJ was entering and backtracking runway 08. While backtracking runway 08 (position 2 on Figure 2), ZZJ’s flight crew heard a broadcast that WOT was joining the circuit as number 2 to the training aircraft and then observed a third aircraft appear on their traffic collision avoidance system (TCAS) display. The captain of ZZJ asked the first officer to contact the third unknown aircraft.

When the pilot flying IOA heard a broadcast from ZZJ, which indicated it was directed at them, they responded that they were approaching a 3 NM final for runway 14 and ZZJ would have time to depart from runway 08 if they were quick. At about this time, ZZJ was approaching the threshold of runway 08. The captain lined ZZJ up for departure and the crew completed their pre-take-off checklist items (three items). At about this time, another two aircraft, 20 NM away from Horn Island, started communicating with each other on the Horn Island CTAF.

By the time the pilot flying IOA heard ZZJ broadcast ‘rolling for departure from runway 08’, IOA was at about 400 ft on final approach for runway 14. The pilot of IOA reported that at about 300 ft, they broadcast ‘hold short’ to ZZJ. However, the captain of ZZJ reported they heard the pilot of IOA say ‘land and hold short of runway 08’.[2] Consequently, ZZJ continued their take-off. As IOA approached 100–150 ft on final approach, ZZJ had not crossed the runway intersection and the pilot flying IOA conducted a left climbing turn away from the runways to join the downwind circuit leg for runway 08. The captain of ZZJ looked out their left window when they were in the initial climb overhead the threshold of runway 26 and saw IOA turning through east at about the same level (position 4 on Figure 2). IOA then joined the circuit for runway 08 and landed after WOT without further incident.

Figure 2: Sequence of movements

Figure 2: Sequence of movements

Source: Google earth, annotated by ATSB

Horn Island Airport and CTAF

The Horn Island Airport is located at the northern end of Cape York Peninsula. The airport acts as the hub for access to the outer islands in the Torres Strait. Mainland services fly into Horn Island and passengers are then transferred onto the local operators’ smaller aeroplanes and helicopters for transfer to and from the outer islands. Runway 08/26 is the main runway and runway 14/32 is shorter and narrower. Smaller aircraft, such as IOA, operate to both runways, but larger aircraft, such as ZZJ, restrict their operations to runway 08/26.

The airport apron is located adjacent to the threshold of runway 32 and there are no taxiways to separate ground movements from aircraft taking off and landing. There is also higher terrain located to the southeast of the airport, which has resulted in the following additional restrictions to airport movements published in the Horn Island aerodrome chart:

Take-off runway 14 and landing runway 32 not permitted due terrain.

Consequently, the smaller local aeroplane operators’ have adopted the local practice of departing from runway 08 and landing on runway 14, weather conditions permitting.

The CTAF boundary extends laterally to 40 NM from Horn Island, which encapsulates the outer islands, and vertically from the surface to 8,500 ft.

ZZJ TCAS settings

The flight crew on board ZZJ had their TCAS set to the 12 NM range scale while backtracking runway 08. The captain reported that they could have improved their picture of the relative bearing and distance of IOA if they reduced the scale to 6 NM while backtracking runway 08. However, their normal procedure is to set the 6 NM range scale for controlled airspace and set the 12 NM range scale for departure from a non-controlled aerodrome to improve situational awareness of inbound traffic.

Right of way provision

Civil Aviation Regulation (CAR) 162 lists the rules for prevention of collision. CAR 162 paragraph 8 states:

An aircraft that is about to take-off shall not attempt to do so until there is no apparent risk of collision with other aircraft.

The captain of ZZJ reported that they relied too heavily on their TCAS and did not place sufficient importance on the ‘see’ element within the ‘see-and-avoid’ philosophy of operations at non‑controlled aerodromes. Consequently, they started their take-off before sighting IOA.

Safety analysis

Prior to the near collision event, the flight crew of both aircraft were aware of the presence of the other aircraft and their approximate position. When ZZJ was backtracking runway 08, the captain was conscious of the fact that they were occupying the main runway that was being used by other aircraft in the circuit.

The broadcast from IOA, that ZZJ could depart before IOA landed, supported the motivation of the captain of ZZJ to avoid delaying their departure from runway 08. The captain of ZZJ also relied on an approximate position of IOA from their TCAS when they elected to take-off. However, as reported by the captain, the range scale set on the TCAS was 12 NM, where a 6 NM range scale could have provided a more accurate picture of the relative position of IOA.

During the take-off, the flight crew probably also misheard the broadcast from the pilot in IOA, to hold short of runway 14, and therefore did not reject the take-off. However, it was not determined if the radio broadcast was before or after ZZJ reached their decision speed (V1) to safely reject the take-off.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The captain of ZZJ was motivated to expedite their departure from the main runway, which in conjunction with the broadcast from IOA that they had time to take-off before IOA landed, contributed to them starting their take-off before they sighted IOA.
  • The flight crew probably misheard the broadcast from the pilot of IOA to hold short of runway 14 and did not reject the take-off.
  • IOA and ZZJ made the required CTAF broadcasts and were aware of the approximate position of each other prior to the near collision event.
  • Concurrent operations to different runways at Horn Island are a normal local practice, which is employed to facilitate traffic movements.

ATSB comment

The ATSB notes that the horizontal and vertical dimensions for standard CTAF boundaries are published in the Aeronautical Information Publication (AIP). However, the dimensions for non‑standard CTAF boundaries are currently only published in the Enroute Supplement Chart LOW.

Safety message

This serious incident highlights that pilots and operators need to consider how best to employ and integrate the sources of information available to them in order to develop an accurate mental model of a potential traffic threat. In the ‘see-and-avoid’ environment, radio broadcasts and TCAS information can be used to hone the visual scan to sight other traffic, which might pose a threat.

Further information on safety around non-controlled aerodromes is available from the ATSB website.

Further information on operations at non-controlled aerodromes is available from the Civil Aviation Safety Authority’s website.

safety watch

__________

  1. IOA and ZZJ were both operating under instrument flight rules, which is why IOA received traffic information on ZZJ while operating outside controlled airspace.
  2. Horn Island Airport experienced a temporary loss of power on the day of the incident. None of the transmissions from the incident aircraft were captured on the available CTAF recorded data.

Aviation Short Investigations Bulletin - Issue 57

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2016-137
Occurrence date 12/10/2016
Location Horn Island Airport
State Queensland
Report release date 09/02/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Near collision
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Pilatus Britten-Norman Ltd
Model BN2A-20
Registration VH-IOA
Serial number 842
Sector Piston
Operation type Charter
Departure point Kubin, Queensland
Destination Horn Island, Queensland
Damage Nil

Aircraft details

Manufacturer Bombardier Inc
Model DHC-8-202
Registration VH-ZZJ
Serial number 551
Sector Turboprop
Operation type Aerial Work
Departure point Horn Island, Queensland
Destination Cairns, Queensland
Damage Nil

Tail skid contact involving a Boeing 777, 9V-SYG, Melbourne Airport, Victoria, on 9 October 2016

Final report

Report release date: 27/04/2017

What happened

On 9 October 2016, a Singapore Airlines Boeing 777-312 aircraft, registered 9V-SYG (SYG), was operating a scheduled passenger service from Melbourne Airport, Victoria, to Singapore with two flight crew, 16 cabin crew and 261 passengers.

The crew arrived on board the aircraft and commenced their standard pre-flight procedures. The captain was operating as pilot flying (PF) and the first officer operating as pilot monitoring (PM).[1] The captain commenced the flight deck pre-flight procedures while the first officer performed the exterior inspection. After completion of the external inspection, the first officer commented to the captain that while on the apron ‘they had difficulty walking straight due to the strong wind’. The flight crew received the automatic terminal information service (ATIS)[2] using the aircraft communication addressing and reporting system. ATIS W advised wind conditions at Melbourne Airport were 325°at 25 kt, gusting to a maximum of 45 kt, and turbulence had been reported in the control zone.

Both flight crew reviewed the load sheet and independently performed take-off performance calculations in accordance with normal procedures. The figures from these calculations were correctly programmed into the aircraft’s flight management computer. The flight crew stated that, in accordance with the operator’s standard operating procedures, they briefed the use of full climb thrust after becoming airborne to mitigate the strong and gusty wind conditions.

At about 1120 Eastern Daylight-saving Time (EDT), the aircraft was pushed back and taxi was commenced. The flight crew stated that while taxiing to the runway 34 holding point, they observed two aircraft on approach to runway 34 perform go-arounds. Both flight crew recalled hearing another aircraft query the tower controller if windshear was reported by the flight crew of the go-around aircraft. The tower controller stated, ‘no windshear, just unstable conditions’. Two aircraft departed prior to SYG with the tower controller again advising the departing aircraft that no windshear was reported. At about 1145, SYG was then cleared for take-off from the full length of runway 34.

During the take-off run, both flight crew recall observing airspeed fluctuations on the airspeed indicator due to wind gusts. Both flight crew stated that, in their opinion, they considered the aircraft’s acceleration rate to be normal during the take-off run. At the calculated rotation speed (Vr),[3] the PF initiated the aircraft rotation. During rotation, the PM observed a downward speed trend, below Vr on the ASI and called ‘SPEED’. The PF did not recall hearing this callout. The PF continued rotation, however, the aircraft did not achieve lift-off at the manufacturer’s stated lift‑off attitude (7 degrees). Flight data analysis shows the aircraft became airborne at 10.7 degrees pitch[4] attitude (see Flight data analysis).

After take-off, air traffic control contacted the flight crew alerting them of a ‘possible tail strike’. With no TAIL STRIKE caution message displayed on the engine indication and crew alerting system[5] the flight crew carried out the unannunciated tail strike non-normal checklist and determined the aircraft structural integrity was intact. The flight crew then referred to the operator’s supplementary procedures for further guidance.

An inspection of the runway identified contact marks, consistent with a tail skid contact. No metallic debris was observed on the runway. Air traffic control advised the flight crew that ‘only superficial concrete debris was found’ during the runway inspection. The captain communicated with the in-flight supervisor who reported back to the captain that cabin crew stationed at the rear of the aircraft heard a ‘loud bang’ during take-off.

The flight crew discussed all the available information and considered their options. With the aircraft pressurisation system indicating no abnormalities the captain made the decision to continue to the destination. This decision was supported by manufacturer’s recommended action to continue to operate normally in the case of an unannunciated tail strike in the B777-300 aircraft.

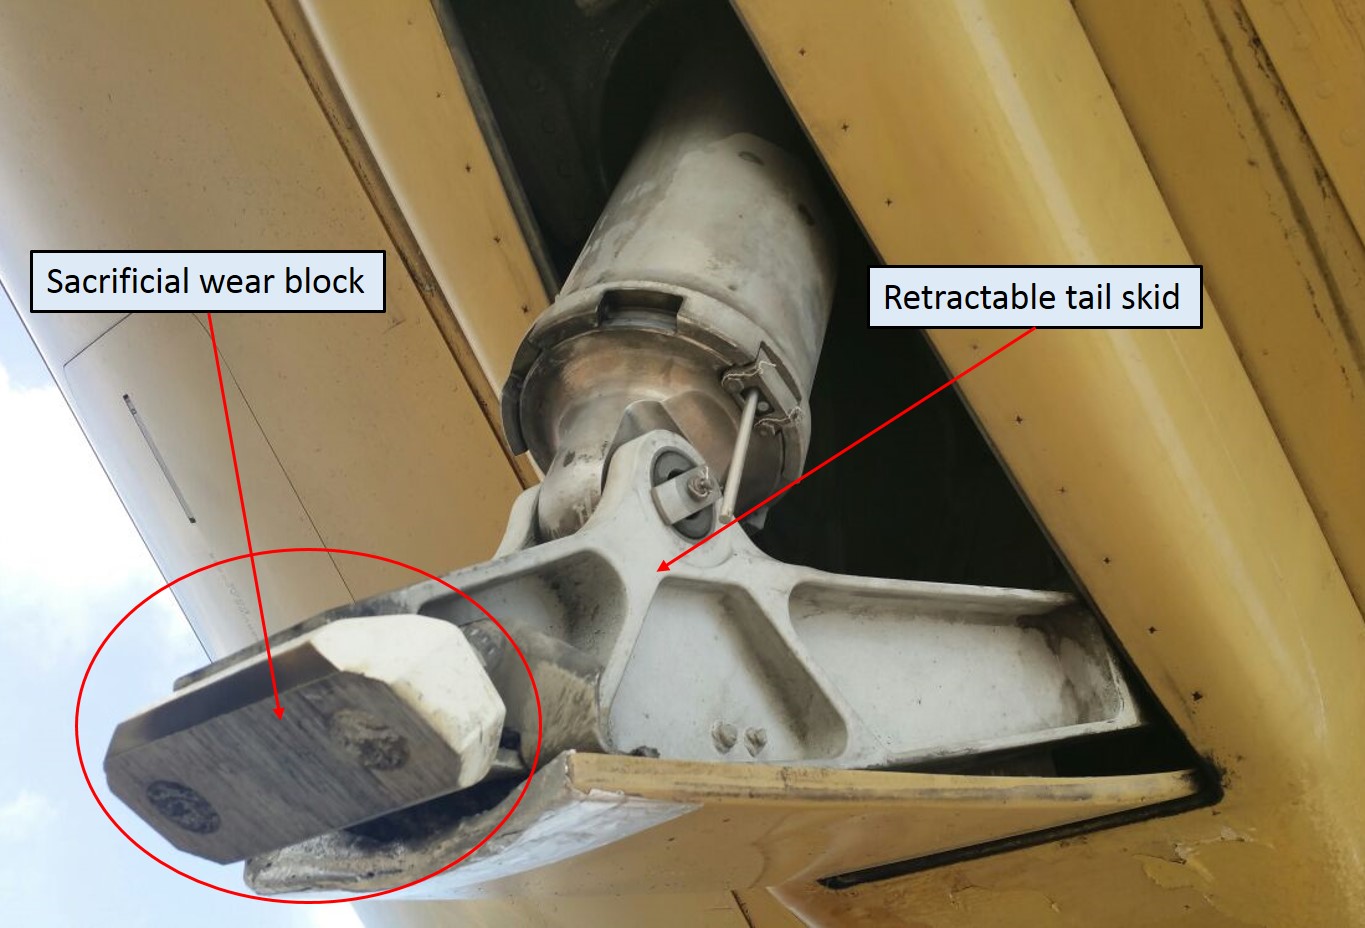
Subsequently, an uneventful landing was carried out in Singapore. Engineers conducted a post-incident inspection of the aircraft and found no damage to the aircraft fuselage. Damage was evident to the tail skid system with indications of a scraped tail shoe, compression of the crushable cartridge and one indicator pin extended (Figure 1).This damage indicated that a moderate energy skid contact had occurred during take-off.

Figure 1: Damage to tail skid

Tail skid displaying erosion to the sacrificial wear block


Source: Singapore Airlines, modified by the ATSB

Safety analysis

Flight data analysis

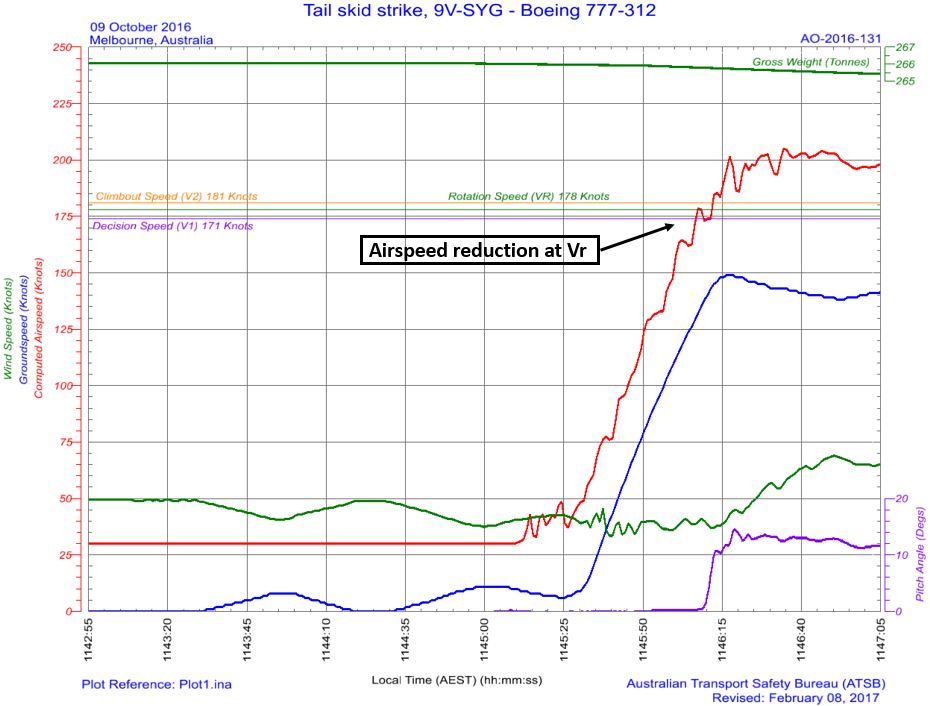
Analysis of the aircraft flight data showed multiple instances of airspeed stagnation from 77 kt computed airspeed through rotation initiation at 178 kt (Vr = 178 kt) and initial climb. Rotation was initiated at a computed airspeed of 178 kt (at Vr) at approximately 0.5 degrees per second initially before increasing to approximately 3 to 4 degrees per second. As rotation was initiated, the headwind component decreased 12 kt, the computed airspeed stagnated and reduced to 173 kt (Figure 2). Lift-off occurred at a pitch attitude of 10.7 degrees. The tail skid contact attitude is 8.9 degrees.

Figure 2: Flight data plot including computed airspeed, and rotation speed (Vr) and pitch attitude

Figure 2: Flight data plot including computed airspeed, and rotation speed (Vr) and pitch attitude

Source: Aircraft operator analysed by ATSB

Wind and airspeed

After reaching rotation speed (Vr), the aircraft’s airspeed reduced by about 5 kt due to a reduction in headwind of about 12 kt.

Continued rotation

The PF reported not hearing the PM call of speed after the PF had rotated the aircraft. If the PF was aware of the speed reduction, the standard procedure, described in the operator’s Flight Crew Training Manual (FCTM), was to momentarily delay rotation. The PF reported that they thought the rotation was normal in the conditions.

Tail skid strike

The aircraft did not become airborne at the manufacture’s pitch attitude of 7 degrees, leading the PF to continue increasing the pitch attitude to 10.7 degrees where lift-off was achieved. This increased pitch attitude exceeded the 8.9 degrees attitude for where a tail strike will occur in the Boeing 777-300 aircraft.

Guidance to flight crew

The operator’s Flight Crew Operations Manual (FCOM) stated that the use of reduced thrust is standard procedure for take-off. The FCOM also listed the environmental conditions when take-offs with reduced thrust are not permitted.

The operator’s FCOM does not contain direct guidance regarding take-off thrust setting requirements in gusty wind and strong crosswind conditions. Guidance for considering the use of higher thrust settings and rotation speeds for take-offs under these environmental conditions is provided in the Flight Crew Training Manual (FCTM).

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The tail skid contact was a result of airspeed stagnation due to gusty atmospheric conditions which prolonged the time to lift-off, allowing the pitch attitude to exceed the tail skid contact attitude.
  • The use of a higher take-off thrust setting would most likely have reduced the required runway length and minimised the aircraft exposure to gusty atmospheric conditions during rotation and lift-off.

Safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following safety action in response to this occurrence.

Flight Operations

As a result of this occurrence, Singapore Airlines has advised the ATSB that they are taking the following safety actions:

Action taken by Singapore Airlines

As a result of this incident, the aircraft operator issued circulars to all company flight crew directing operation towards Boeing’s recommendation of the use of higher thrust and rotation speed for take-off in gusty wind and strong crosswind conditions.

Safety message

This incident serves as a reminder to Boeing pilots that guidance material contained in manuals outside the FCOM should be considered in all aircraft operations. The use of a higher thrust setting as recommended by the Boeing FCTM would have reduced the required runway length and minimised the airplane exposure to gusty conditions during rotation, lift-off and initial climb. Boeing also states that the use of a higher take-off rotation speed, if take-off performance permits, can increase the tail clearance margin during the rotation.

While taking the above message into consideration, this incident provides an excellent example of flight crew managing a non-normal operation. Throughout the non-normal occurrence period, the flight crew communicated with each other, air traffic control and the cabin crew, which allowed all relevant information available to be gathered. The flight crew demonstrated effective crew resource management and decision making resulting in the flight being able to continue to destination without compromising safety.

Aviation Short Investigations Bulletin - Issue 59

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

__________

  1. Pilot Flying (PF) and Pilot Monitoring (PM): procedurally assigned roles with specifically assigned duties at specific stages of a flight. The PF does most of the flying, except in defined circumstances; such as planning for descent, approach and landing. The PM carries out support duties and monitors the PF’s actions and the aircraft’s flight path.
  2. Automatic Terminal Information Service (ATIS). The provision of current, routine information to arriving aircraft and departing aircraft by means of continuous and repetitive broadcasts.
  3. VR: the speed at which the rotation of the aircraft is initiated to take-off attitude. This speed cannot be less than V1 or less than 1.05 times VMCG. With an engine failure, it must also allow for the acceleration to V2 at a height of 35 ft at the end of the runway.
  4. Pitch: the motion of an aircraft about its lateral (wingtip-to-wingtip) axis.
  5. Engine Indication and Crew Alerting System (EICAS) consolidates engine and airplane system indications and is the primary means of displaying systems indications and alerts to flight crew.

Occurrence summary

Investigation number AO-2016-131
Occurrence date 09/10/2016
Location Melbourne Airport
State Victoria
Report release date 27/04/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Ground strike
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 777-312
Registration 9V-SYG
Serial number 28528
Aircraft operator Singapore Airlines
Sector Jet
Operation type Air Transport High Capacity
Departure point Melbourne, Victoria
Destination Singapore
Damage Minor

Engine failure involving Fairchild SA227, VH-VEU, 170 km south of Brisbane, Queensland, on 12 October 2016

Final report

Report release date: 09/02/2017

What happened

On 12 October 2016, a Vee H Aviation Fairchild Industries Inc. SA227-DC, registered VH-VEU, conducted a regular public transport flight from Armidale, New South Wales, to Brisbane, Queensland. On board the flight were two flight crew and 13 passengers. The captain was the pilot flying (PF) and the first officer was the pilot monitoring (PM).[1]

At 0755 Eastern Daylight-saving Time (EDT), the aircraft was about 170 km south of Brisbane, cruising at FL 170,[2] when the aircraft suddenly yawed to the right.[3] The PF re-stated they had command of the aircraft and directed the PM to identify the failure. The flight crew then employed their ‘identify and confirm’ crew resource management (CRM) procedures to confirm the right engine was not delivering power and then shut down the right engine and feathered the right propeller.[4] During the diagnosis, the PM noted that all right engine indications were normal except for a low torque reading (10%) and low fuel flow (140 pounds per hour).

Air traffic control contacted the crew to confirm they were maintaining FL 170 and the PM responded with a PAN broadcast[5] that they were descending due to a right engine failure. The crew reviewed their options and decided to continue to Brisbane Airport. They completed the remaining checklist actions and briefed the passengers. The crew then requested, and were given, a direct track to Brisbane Airport from air traffic control. They completed their normal and single engine landing checklist procedures and landed at Brisbane Airport runway 19 without further incident.

Maintenance findings

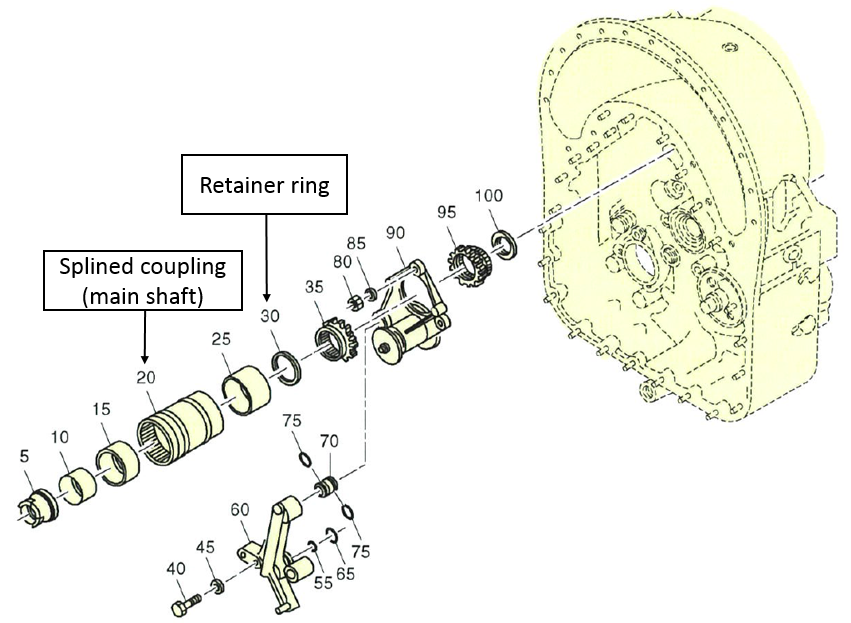
The engine installed in the aircraft was the Honeywell (previously Garrett) TPE331-12UHR-701G. The operator’s engine maintenance organisation found a retainer ring within the engine accessory gear assembly had failed, which allowed the main shaft (which drives the propeller) to de-couple from the engine driven reduction gearbox (Figure 1).

The retainer ring was shipped to the maintenance organisation from Honeywell in December 2008 as part of a batch of 10 with a certificate of conformance from the part manufacturer and Honeywell. It was fitted new to the incident engine in December 2009 at the last engine overhaul, about 2,429 hours prior to the failure. The maintenance organisation introduced this practice of replacing the retainer ring at each overhaul based upon their previous service experience of this part failing. December 2009 was the last overhaul of the accessory gear assembly prior to the failure.

In October 2015, Honeywell added temporary revision 72-241 to the maintenance manual procedure: removal and installation of accessory gear assembly, to direct the replacement of the retainer ring at each exposure. Figure 2 depicts the failed retainer ring.

Figure 1: Engine accessory gear assembly

Figure 1: Engine accessory gear assembly

Source: Maintenance organisation, annotated by ATSB

Figure 2: Retainer ring

Figure 2: Retainer ring

Source: Operator

Continuing airworthiness maintenance interval

The operator set their maintenance interval for the incident engine in accordance with the engine manufacturer’s service bulletin for periodic inspections, (Honeywell TPE 331-72-0476). From the service bulletin, the operator set the inspection of the engine at the 7,000 hour continuing airworthiness maintenance (CAM) interval with gearbox inspection, for commercial operations. This included the requirement for the accessory gear assembly inspection in accordance with the maintenance manual procedures at the 7,000 hour interval.

The operator’s spectrometric oil-analysis programme (SOAP analysis) was set at 150 hour intervals at the time of the incident.[6] The previous SOAP analysis was conducted at about 26 hours prior to the failure and did not detect any anomalies. Further information on SOAP is available from Civil Aviation Safety Authority airworthiness bulletin (AWB 79-1): Spectrographic oil analysis program (SOAP).

The gearbox is fitted with a single magnetic drain plug (chip detector).[7] If a metallic particle is detected by the chip detector inflight, it will activate a caution light to advise the flight crew. The inspection interval for the chip detector is set at 300 hours. The last inspection was about 144 hours prior to the incident and no anomalies were found. There were no activations of the chip detector between the last scheduled inspection and the incident flight, and the chip detector did not activate during the incident flight.

The operator also conducts propeller dynamic balance checks at 600 hour intervals. There have been no out-of-limit vibration indications since engine installation. The last check was performed 17 September 2016.

Safety analysis

The operator had several preventive maintenance inspections in place, which included an overhaul of the gearbox, SOAP analysis, magnetic drain plug inspection and propeller dynamic balance. The previous overhaul was about 2,429 hours prior to the failure at which time the retainer ring was fitted new to the gearbox. During the time interval to failure of the retainer ring, the SOAP analysis, magnetic drain plug inspections and propeller dynamic balance checks did not detect any anomalies. Therefore, the failure of the retainer ring was within the required gearbox inspection intervals and without prior warning of an impending failure.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The retainer ring failed within the prescribed maintenance interval.
  • There was no prior warning of an impending failure of the retainer ring.

Safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Operator

As a result of this occurrence and subsequent to an update by the engine manufacturer to the engine manufacturer’s service bulletin, the aircraft operator has advised the ATSB that they are taking the following safety actions:

SOAP analysis

The operator reduced their SOAP analysis interval from 150 hours to 100 hours.

Damaged parts

The damaged parts from the gearbox were sent to the engine manufacturer for analysis.

Safety message

Following the aircraft yaw, the flight crew actively employed their crew resource management procedures to identify and confirm the engine fault and then shut down the right engine. The use of these procedures reduced the risk of an incorrect diagnosis of the fault or activation of the incorrect engine controls during shut down.

__________

  1. Pilot Flying (PF) and Pilot Monitoring (PM): procedurally assigned roles with specifically assigned duties at specific stages of a flight. The PF does most of the flying, except in defined circumstances; such as planning for descent, approach and landing. The PM carries out support duties and monitors the PF’s actions and the aircraft’s flight path.
  2. Flight level: at altitudes above 10,000 ft in Australia, an aircraft’s height above mean sea level is referred to as a flight level (FL). FL 170 equates to 17,000 ft.
  3. Yawing: the motion of an aircraft about its vertical or normal axis.
  4. Feathering: the rotation of propeller blades to an edge-on angle to the airflow to minimise aircraft drag following an in-flight engine failure or shutdown.
  5. PAN PAN: an internationally recognised radio call announcing an urgency condition which concerns the safety of an aircraft or its occupants but where the flight crew does not require immediate assistance.
  6. SOAP is a method to test the health of engines by performing laboratory testing of the engine oil. A sample of oil showing an increase in parts per million of iron material could be a warning of impending failure. The chemical composition of any metal particles in the oil sample is compared to various engine parts to detect the location of abnormal wear.
  7. A chip detector is a device, often a permanent magnet, for gathering metal chips from the engine oil to provide early warning of an impending failure. A magnetic drain plug is a removable chip detector.

Aviation Short Investigations Bulletin - Issue 57

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2016-136
Occurrence date 12/10/2016
Location 170 km south of Brisbane
State Queensland
Report release date 09/02/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Engine failure or malfunction
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Fairchild Industries Inc
Model SA227-DC
Registration VH-VEU
Serial number DC-797B
Sector Turboprop
Operation type Charter
Departure point Armidale, New South Wales
Destination Brisbane, Queensland
Damage Nil

Birdstrike and inflight vibration involving Boeing 747-438 ER, VH-OEH, near San Francisco International Airport, United States, on 6 October 2016

Final report

Report release date: 29/06/2017

Safety summary

What happened

On 6 October 2016, a Boeing 747-438 ER, registered VH-OEH and operated by Qantas International, departed San Francisco International Airport, United States, for a flight to Sydney, Australia. Soon after departure and during the climb, the crew became aware of an abnormal vibration in the area of the left over-wing door. There were no cockpit indications or associated procedures to manage the observed vibration. Consequently, the flight crew were required to use their professional judgement to assess its impact on the flight. The crew utilised available crew resources and maintenance expertise to troubleshoot and assess that the flight could safely continue to Sydney.

What the ATSB found

The ATSB found that during departure from San Francisco International airport, and unbeknown to the flight crew, the aircraft sustained impact damage from a birdstrike. The birdstrike sheared a landing gear door strut resulting in the door not closing. That in turn led to turbulent airflow and in‑cabin vibration.

What’s been done as a result

While the birdstrike resulted in a landing gear door not closing, the overall impact on the flight was minimal. Larger doors that have the potential to cause damage have warning systems to indicate if they have not operated as selected.

There was no additional wear or damage to any of the landing gear components. The landing gear door strut was replaced and the aircraft returned to service.

Safety message

This occurrence highlights that, even with the assistance of sophisticated technology and systems, flight crew may experience situations that can only be managed using their professional judgement.

In this case, the flight crew utilised the support of both on-ground maintenance personnel and cabin crew to methodically troubleshoot the source of the vibration and assess that the flight could be safely continued to the destination airport.


The occurrence

At about 2335 local time on 6 October 2016, a Boeing 747-438 ER, registered VH-OEH and operated by Qantas International, departed San Francisco International Airport, United States, for a flight to Sydney, Australia. The flight crew reported that the night departure was uneventful.

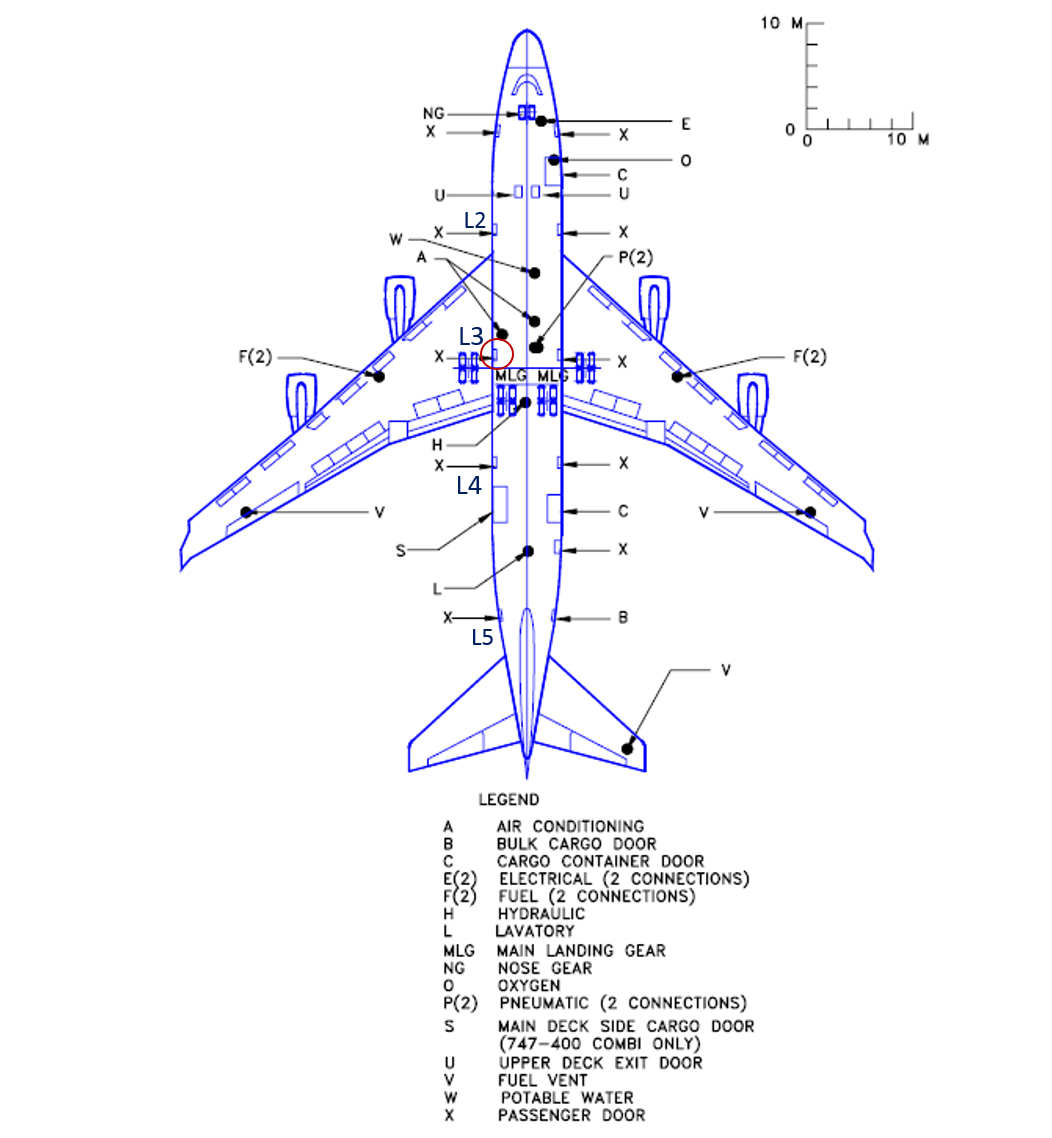
Soon after take-off, the cabin services manager (CSM) was contacted via the aircraft interphone system by a cabin crew supervisor seated near door L3 (Figure 1). The supervisor advised the CSM that there was vibration and louder than normal cabin noise in their area. The CSM recalled that following receipt of that advice from the supervisor, they also became aware of the increased noise.

A training captain seated in the flight deck, also reported being aware of a louder than normal noise during the climb. The captain under training was new to the aircraft type and therefore did not notice the additional noise.

As the aircraft approached top of climb, and after the flight crew had turned off the fasten seatbelts sign, the CSM contacted the flight crew to report the additional noise/vibration. As indications on the flight deck were normal, the second officer was sent to investigate the source of the vibration.

The second officer inspected several sections of the cabin in consultation with the CSM and other flight attendants. They concluded the magnitude of the vibration was largest near door L3 (rows 47-49, seats ABC) and that it was considerably noisier than normal. The CSM recalled that the second officer suspected the vibration may have been due to a landing gear door seal. Unlike other large passenger aircraft, VH‑OEH did not have installed video cameras that permitted the crew to view external parts of the aircraft. In any event, the night conditions may have hampered visual examination of the landing gear area on this occasion. The second officer returned to the flight deck and briefed the other flight crew.

About 2 hours into the flight, the flight crew contacted the company’s maintenance operational control (MOC) centre via satellite phone seeking technical assistance to identify the source of vibration. The flight crew relayed the relevant information to the duty manager, a senior aircraft engineer, who then asked additional questions to assist with the diagnosis. The MOC duty manager advised the crew that it could be a gear door seal or wing-to-body seal as they were located in that area.

The MOC duty manager subsequently checked the:

  • aircraft history for any similar faults/reports, of which there were none
  • relevant aircraft system diagrams to ascertain what systems were located near door L3 and capable of generating the reported vibration/noise
  • relevant maintenance manual section covering possible sources of airframe vibrations.

The flight crew, in consultation with the MOC duty manager and cabin crew, then systematically went through a process of trying to isolate the source of the vibration/noise.

That process included isolation and/or consideration of:

  • the aircraft air-conditioning packs
  • the air recirculation fans
  • re-selection of the landing gear handle to the UP position
  • checking toilets for possible vacuum leaks.

That troubleshooting was unable to isolate the source of vibration and noise. The flight crew requested that the cabin crew continue to monitor the vibration/noise and to advise them of any change. As the aircraft was otherwise performing normally, the flight was continued.

About 4.5 hours into the flight and with no reported change to the vibration/noise levels, the training captain left the flight deck to personally assess the vibration and assessed that it was still quite noisy. Consequently, the flight crew again made contact with the MOC to seek further technical input. They asked the duty manager what other aircraft systems were in the L3 door area. The duty manager advised that there were hydraulics and centre fuel tank transfer pumps. While the crew could not isolate the hydraulics, the transfer pumps were OFF.

The duty manager advised the crew that maintenance services were available at the now nearby Honolulu Airport, Hawaii and enquired if the crew wished to divert. The crew advised the MOC that they did not intend to divert at that stage. The training captain reported to the ATSB that, as the aircraft was otherwise performing normally, it was not considered necessary to divert from the original destination.

The flight crew, with the assistance of the cabin crew, continued to monitor the vibration (which remained constant) and the flight continued to Sydney. They also remained in contact with the MOC.

Figure 1: Aircraft schematic showing location of door L3 (circled red) and other services

Figure 1: Aircraft schematic showing location of door L3 (circled red) and other services

Source: Boeing Commercial Airplanes

The CMS reported that the vibration and noise persisted up until the landing gear was extended during the approach into Sydney. The cabin crew did not receive any comments about the vibration or noise from the passengers.

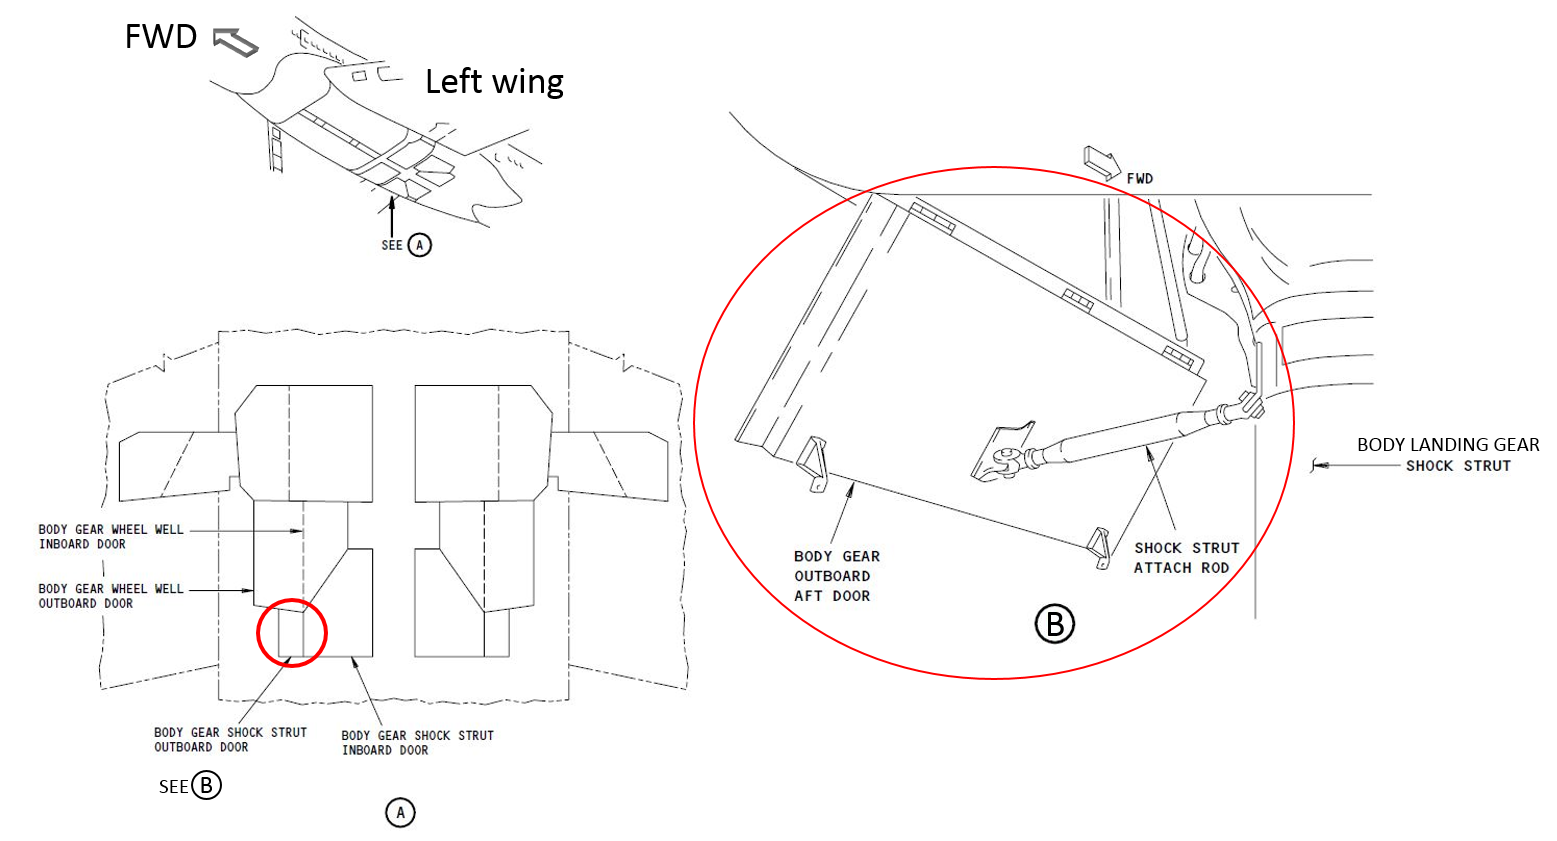
After landing, ground engineers inspected the aircraft and immediately identified a protruding landing gear seal and initially thought this was the source of the vibration. On closer examination they observed that a rod, which normally attaches a small outboard landing gear door to the body landing gear shock strut (Figure 2), was sheared at the door attachment point as a result of a birdstrike.

Despite the door not being closed during the flight, there was no additional wear or damage. The attach rod was replaced, and the aircraft returned to normal service, with no further vibration or noise reported.

Figure 2 Main landing gear doors showing location of affected door and attach rod.

Figure 2 Main landing gear doors showing location of affected door and attach rod.

Source: Boeing Commercial Airplanes

Safety analysis

Due to the physical size of the aircraft and the night departure, the birdstrike was not detected by the flight crew or ground personnel. Given the vibration was first noticed following retraction of the landing gear, it could be argued that the vibration was therefore directly related to the landing gear. However, all indications were that the landing gear had retracted normally. In addition, as there is significant additional noise and vibration while the landing gear is extended, it is equally plausible that this noise may have been masking something unrelated to the landing gear.

While the training captain was aware of some additional noise during the climb, all flight deck indications were normal including those for the landing gear. Due to sterile cockpit procedures, that limited other than emergency communications during critical phases of flight, the first indication that there was something abnormal was when the cabin services manager contacted the flight deck.

Once the nature and location of the vibration had been established, the flight crew proceeded to make use of all available resources to try and identify the source of the vibration and its implication for the continuation of the flight. In consultation with both maintenance operational control and cabin crew, the crew systematically isolated systems capable of generating the vibration. While they were unable to identify the source of the vibration, the flight crew established that it was constant and that the aircraft was otherwise performing normally. In the absence of any abnormal flight deck indications or relevant checklist, the decision to continue the flight was therefore at the discretion of the flight crew based on their professional judgement.

The landing gear system on the Boeing 747 uses a combination of hydraulics and attach rods to extend/retract both the landing gear and the associated doors. Proximity switch sensors located on both the landing gear and the hydraulically operated doors provide the flight crew with indications of both normal and abnormal operation. Small doors that are attached by rods directly to the landing gear, do not have proximity sensors as they normally open and close with the landing gear.

The discovery of the sheared attach rod, evidence of a birdstrike, and the reported in-flight vibration, is consistent with the aircraft having sustained a birdstrike during the departure and while the landing gear was extended. Due to the sheared attach rod, the associated landing gear door would not have closed resulting in residual turbulence and vibration being generated in the area of door L3. The lack of an associated proximity sensor meant that the flight crew were unaware that the door was not closed.

Findings

From the evidence available, the following findings are made with respect to the birdstrike and inflight vibration involving Boeing 747, registered VH-OEH near San Francisco International Airport, United States on 6 October 2016. These findings should not be read as apportioning blame or liability to any particular organisation or individual.

Contributing factors

  • During departure from San Francisco International airport, and unbeknown to the flight crew, one of the main landing gear door struts sustained impact damage from a birdstrike that resulted in the associated landing gear door not closing.

Other findings

  • The noise and vibration experienced in the cabin was due to turbulent airflow associated with the un-closed landing gear door.
  • The absence of cockpit indications and/or associated procedures to manage the observed vibration meant that the flight crew were required to use their professional judgement to assess its impact on the flight. The crew utilised available crew resources and maintenance expertise to troubleshoot and assess that the flight could safely continue to the destination airport.

Sources and submissions

Sources of information

  • The sources of information during the investigation included the:
  • flight crew
  • cabin crew
  • maintenance personnel
  • aircraft operator and manufacturer.

Submissions

  • Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
  • A draft of this report was provided to the aircraft operator, flight crew, cabin services manager, maintenance operational control duty manager and the Civil Aviation Safety Authority (CASA).
  • Submissions were received from CASA, the aircraft operator and maintenance personnel. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2016-135
Occurrence date 06/10/2016
Location Near San Francisco International Airport, United States
State International
Report release date 29/06/2017
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Airframe - Other
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 747-438
Registration VH-OEH
Serial number 32912
Aircraft operator Qantas Airways
Sector Jet
Operation type Air Transport High Capacity
Departure point San Francisco, United States
Destination Sydney, New South Wales
Damage Minor

Wheels up landing involving Cessna 210, VH-UPN, Broome Airport, Western Australia, on 10 October 2016

Final report

Report release date: 17/01/2017

What happened

At 1433 Western Standard Time (WST), on 10 October 2016, a Cessna 210N aircraft, registered VH-UPN (UPN), departed Fitzroy Crossing, Western Australia (WA), for a passenger charter flight to Broome Airport, WA. On board were a pilot and three passengers.

At about 80 NM from Broome, the pilot began a descent from the cruising altitude of 8,500 ft. At 1540, as the aircraft approached 15 NM from Broome, Broome air traffic control (ATC) cleared UPN to conduct a straight-in approach to runway 28. The pilot manoeuvred the aircraft to join a 10 NM final approach to runway 28.

At 1545, passing 5 NM from Broome Airport, the pilot reported they levelled the aircraft at 1,000 ft and conducted the pre-landing checklist in accordance with operator procedures. The pre-landing checklist included selecting the landing gear down and confirming that the landing gear was extended. At about 1547, an individual located under the approach path to runway 28, about 800 m from the runway 28 threshold, observed a Cessna 210 on approach with the landing gear retracted. The individual contacted a member of Broome Airport operations to notify them of the sighting, however, the notification was not received until after the incident.

At 1548, the aircraft touched down on runway 28 with the undercarriage retracted (Figure 1). The aircraft slid along the runway on the underside of the fuselage before stopping. After the aircraft stopped, the pilot contacted ATC to request assistance. The pilot then raised the flaps to provide a clear evacuation path for the passengers. After raising the flaps, the pilot shut the aircraft down, selected fuel off and assisted the passengers with exiting the aircraft.

No persons were injured in the incident and the aircraft sustained minor damage.

Figure 1: UPN after the wheels-up landing

Figure 1: UPN after the wheels-up landing

Source: Aircraft operator

Pilot comments

The pilot of UPN provided the following comments:

  • The pilot’s roster required them to operate both the fixed landing gear Cessna 206 and the retractable landing gear Cessna 210. They found this difficult and felt that this may have contributed to the landing gear not being selected down prior to landing.
  • Prior to departure, the pilot operated a flight from Broome to Fitzroy Crossing. The pilot initially planned to spend 30 minutes at Fitzroy Crossing, however late passengers delayed departure by about 50 minutes. The temperature at Fitzroy Crossing during this time was 41 degrees. The pilot was able to spend about 10 minutes of this time in an air-conditioned caravan, but the rest of the time was spent outside in the heat. A full bottle of water was consumed during this time, however, at the time of departure the pilot reported feeling agitated and slightly dehydrated.
  • Prior to landing, as the aircraft passed over the runway threshold, at a height of about 50-100 ft, the pilot reduced engine power to idle. The pilot reported that they did not hear the landing gear unsafe warning horn prior to the landing.
  • The pilot may have only completed the pre-landing checklist mentally without actually performing the required actions.
  • The pilot felt that ATC personnel should have checked to confirm that the aircraft’s landing gear was extended prior to the aircraft landing.
  • While shutting down and securing the aircraft after the incident, the pilot may have selected the landing gear down.
  • After exiting the aircraft, the pilot observed the landing gear to be slightly extended and resting on the runway surface.

Operator report

The operator provided a report with the following comments:

  • An engineering inspection conducted after the incident found no fault with the landing gear system or landing gear unsafe warning system.
  • The damage to the underside of the fuselage and absence of damage to the landing gear indicated the landing gear was fully retracted during the landing.
  • After the landing, the propeller pitch control was found approximately 5 cm from the high-RPM position, the fuel selected off, the flaps retracted and the landing gear selector in the down position.
  • During straight in approaches, pilots are trained to select landing gear down at 5 NM from the destination airport and to complete the pre-landing checks at 3 NM if not already complete. Once established on final approach, pilots are trained to conduct a final check. This final check includes selecting the propeller pitch control to high-RPM, confirming the undercarriage is selected down and selecting full flaps. The final check is not included in the company operating procedures or aircraft checklists.
  • The pilot was wearing a noise cancelling type headset, which may have prevented them from hearing the landing gear unsafe warning horn.
  • Broome Airport ATC personnel did not detect that the landing gear had not been extended.

Landing gear warning system

The Cessna 210 is fitted with a landing gear warning system. This system is designed to help prevent a pilot landing with the landing gear retracted. The system will activate when engine power is reduced below about 12 inches of manifold pressure and the landing gear is not down and locked. When activated, the system emits an intermittent tone through the cabin speaker.

Air traffic control procedures

The provider of air traffic services within Australia, Airservices Australia, procedures require a controller to confirm the undercarriage is extended for a civil aircraft when:

  • Doubt exists as to whether the aircraft’s landing gear is fully extended.
  • Issuing a landing clearance to a general aviation aircraft with retractable undercarriage that has experienced abnormal operation.
  • The controller on duty at the time of the incident acted in accordance with ATC procedures. The controller also reported that they checked the aircraft while it was on final approach and did not detect anything unusual.
  • Airservices Australia advised that if anything unusual is detected by a controller, the pilot in command will be notified.

Safety analysis

The aircraft was observed on final approach with the landing gear retracted. The pilot commented that after exiting the aircraft the landing gear was found sagging against the runway surface. However, the absence of damage to the nose landing gear doors and the main landing gear legs and tyres indicated that the landing gear was fully retracted when the aircraft landed.

The propeller control was found positioned about 5 cm from the high RPM position required by the final approach check. This was a position consistent with a cruise and approach setting. Therefore, the pre-landing checklist and final approach check were likely not completed resulting in the aircraft landing with the landing gear selected up.

The operator did not have a documented distance from the airport by which the pre-landing checklist should be completed and the final approach check had also not been documented. Such measures increase the chance a pilot will detect incomplete pre-landing checks.

The pilot reported that they did not hear the landing gear warning system prior to the landing. The pilot reduced engine power to idle at a height of about 50-100 ft and glided to the landing. The system should have activated to alert the pilot to the retracted landing gear. The pilot’s noise-cancelling headset may have prevented the landing gear warning tone from being heard.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The pilot did not complete the pre-landing checklist and the final approach checks resulting in the aircraft landing with the landing gear retracted.
  • The operator’s procedures did not define a distance where the pre-landing checks should be completed and the final approach checklist was not documented.
  • The landing gear warning system did not alert the pilot to the retracted landing gear, probably as the pilot was wearing a noise-cancelling headset.

Safety action

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Aircraft Operator

As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety actions:

Change to operating procedures

The final approach check has been added to the company operating procedures and aircraft checklists and a distance has been added to the pre-landing checklist to specify when the pre-landing checks should be completed.

Pilot training

Company pilots have been reminded to confirm the position of the landing gear during the pre-landing and final approach checks on all company aircraft, regardless landing gear type. This assists in building well established routines for operating aircraft with retractable landing gear.

Safety message

This incident provides a good example of the importance of checklist vigilance. Checklists are designed to ensure that flight crew properly configure the aircraft for any given phase of flight. Regular routine flying can lead to checklists, which are regularly completed, being conducted mentally without the required actions being completed. Vigilance is required to ensure that each checklist is completed correctly and in full.

Pilots should also familiarise themselves with the expected performance of an aircraft for a given power setting, configuration and loading. Extending the landing gear creates an increase in drag which must be balanced by an increase in engine power to maintain a given flight path. When aircraft performance deviates from expectations this may be an indication that aircraft configuration is not correct, such as landing gear remaining retracted when the phase of flight requires it to be extended. This should act as a trigger for the pilot to confirm the configuration of the aircraft.

The Flight Safety Australia article Those who won’t: avoiding gear-up landings includes the following information to assist pilots in avoiding gear up landings:

Most retractable landing gear aeroplanes have landing gear warning systems, but there are normal flight situations where warning systems won’t help.

For instance, most gear warning horns are rigged to sound when the throttle is brought to idle if the gear is not down. But if you use power to touchdown, which many pilots do in windy conditions, or to cushion even a normal landing, the gear warning horn will not sound. In some aeroplanes the gear warning also sounds if the flaps are fully down when the gear is not. This warning only works, however, if you select full flaps. Some pilots don’t use full flaps for every landing, especially in windy conditions, and in these cases the warning will not sound.

In some aeroplanes the gear warning also flashes an annunciator on the instrument panel. Pilots generally focus their attention outside the aeroplane on final approach, however, and may not see a cockpit warning. Conditions that prevent the gear warning horn from sounding will also inhibit the annunciator light.

If you make full-stall landings you get used to hearing the stall warning horn on touchdown. You may not notice the difference between a steady stall warning and the intermittent gear advisory.

Lastly, modern noise-cancelling headsets often prevent the pilot from hearing a warning horn, unless the aeroplane has been modified to pipe the warning through the intercom.

Aviation Short Investigations Bulletin - Issue 56

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

Occurrence summary

Investigation number AO-2016-134
Occurrence date 10/10/2016
Location Broome Airport
State Western Australia
Report release date 17/01/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Wheels up landing
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Cessna Aircraft Company
Model 210N
Registration VH-UPN
Serial number 21064125
Sector Piston
Operation type Charter
Damage Minor

Accredited representative to the United States National Transportation Safety Board investigation of the collision with terrain involving Fokker DR-1, registered N83WR, at Fulshear, Texas, United States, on 3 October 2016

Summary

On 8 October 2016 the ATSB was advised that the United States National Transportation Safety Board (NTSB) had commenced an investigation into a collision with terrain involving a Fokker DR-1 aircraft, registered N83WR. Initial investigation by the NTSB indicated that the aircraft experienced a partial engine power loss shortly after take-off.

As Australia is the State of Manufacture of the engine, on 11 October 2016 the ATSB requested to be appointed as an accredited representative to the NTSB investigation in accordance with clause 5.18 of Annex 13 to the Convention on International Civil Aviation Aircraft Accident and Incident Investigation. An ATSB investigator was appointed as accredited representative to the NTSB investigation on 12 October 2016. To facilitate support to the NTSB investigation, the ATSB also initiated an investigation under the Australian Transport Safety Investigation Act 2003.

The NTSB determined the probable cause of the accident. Details are available on the NTSB website at https://www.ntsb.gov/_layouts/ntsb.aviation/brief.aspx?ev_id=20161006X61204&key=1

Any enquires relating to the investigation should be directed to the NTSB at : www.ntsb.gov

Occurrence summary

Investigation number AE-2016-133
Occurrence date 03/10/2016
Location Fulshear, Texas, USA
State International
Report release date 03/06/2017
Report status Final
Investigation level Defined
Investigation type External Investigation
Investigation phase Final report: Dissemination
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level None

Aircraft details

Manufacturer Amateur Built Aircraft
Model Fokker DR-1
Registration N83WR
Sector Sport and recreational
Operation type Sports Aviation
Departure point Fulshear, Texas
Damage Substantial

Severe turbulence involving Bombardier DHC-8-402, VH-LQM, 30 km south of Canberra Airport, Australian Capital Territory, on 10 October 2016

Final report

Report release date: 17/01/2017

What happened

On 10 October 2016, a QantasLink Bombardier DHC-8-402, registered VH-LQM, conducted a scheduled passenger flight from Melbourne, Victoria, to Canberra, Australian Capital Territory. On board the aircraft were two flight crew, two cabin crew and 70 passengers. The captain was the pilot flying (PF) and the first officer was the pilot monitoring (PM).[1]

During the pre-flight briefing at Melbourne Airport, the flight crew noted there was severe turbulence and severe mountain wave turbulence in the area forecast[2] and SIGMET[3] for their descent and approach to Canberra. They briefed the cabin crew to be prepared for a quick cabin service and that the seat belt sign would be activated early on the approach due to the forecast turbulence.

The aircraft departed from Melbourne at about 1158 Eastern Daylight-saving Time (EDT) and climbed to a cruising level of FL 210.[4] The flying conditions were smooth at FL 210 and the flight was issued with the POLLI FOUR ALPHA standard arrival route into Canberra, which started at waypoint POLLI, to the south west of Canberra (Figure 1). The flight crew instructed the cabin crew to prepare the cabin for landing several minutes before the top of descent. However, the flying conditions continued to be smooth during the descent, so the flight crew waited until about FL 130 before activating the seatbelt sign. This was shortly after passing waypoint POLLI.

Between waypoints GOMAN and HONEY, the aircraft descended below FL 110 and the PF reduced the aircraft speed to 210 kt, which is the best speed for turbulence penetration. The PM estimated that the tailwind component reduced from about 70 kt to about 40 kt after the descent below FL 110. At this point, the aircraft was tracking about 060° and passing in and out of cloud over the Brindabella Ranges, which has ridgelines orientated north-south to the south-west of Canberra.

During the descent, the flight crew did not observe any weather radar indications of potential turbulence or visible indications from the shape or movement of the clouds. Between waypoints HONEY and DALEY at about 7,000 ft AMSL, while passing through a small cloud, the aircraft dropped abruptly. The flight crew reported that everything in the flight deck became airborne, the autopilot disengaged, and the PF struck the left side of their head on the overhead air-vent and light, which dislodged their headset. The captain handed control over to the first officer while they refitted their headset and re-established communications, then resumed their flying pilot role and reset the autopilot.

The flight crew continued the approach to land at Canberra without further incident and notified Canberra air traffic control of their severe turbulence encounter on the approach. After the aircraft landed, the PM contacted the cabin crew to check if there were any cabin injures to report. The cabin crew indicated they were uninjured and made a public address to the passengers to check for injuries. The PM then called their company to inform them the aircraft was unserviceable after a severe turbulence incident, and also noticed the captain’s minor injuries.

During the disembarkation of the passengers, the cabin crew informed the first officer that one passenger had hit their head on the overhead baggage locker. The first officer then asked a company ground agent to contact the emergency services so the passenger could be checked. However, the passenger declined treatment. The emergency services arrived and checked the captain. The captain was then advised by the company to visit a doctor where they were diagnosed with minor injuries.

Figure 1: POLLI FOUR ALPHA arrival track of VH-LQM

Figure 1: POLLI FOUR ALPHA arrival track of VH-LQM

Source: Google earth, annotated by ATSB

Flight data recorder

The flight data recorder showed that as the aircraft descended through about 7,800 ft the aircraft was in a stable descent maintaining 210 kt and heading 042°. As the aircraft descended through about 7,300 ft the airspeed peaked at about 240 kt and the vertical acceleration oscillated rapidly between a maximum of +1.6G,[5] minimum of -1G, then maximum of +1.6G before returning to +1G.

Maintenance inspection

After landing, the captain raised a defect report in the maintenance technical log for the severe turbulence encounter. Inspections were then conducted for the severe turbulence assessment. No defects were found, and the aircraft returned to service on 12 October 2016.

Weather forecast

The weather forecast for the Canberra area, issued for the period from 0840 to 2200 EDT on 10 October 2016 included severe turbulence below 12,000 ft and severe mountain wave turbulence above 5,000 ft. The wind was forecast as follows:

  • 10,000 ft, from 300° at 60 kt
  • 7,000 ft, from 300° at 45 kt
  • 5,000 ft, from 290° at 30 kt.

Mountain waves

Mountain waves may be experienced on the lee-side of mountain ranges as smooth undulating airflow or may contain turbulence in the form of breaking waves and rotors (Figure 2). They typically form when the wind direction is close to perpendicular to a ridge line (+/-30°), the wind speed is at least 15 kt[6] and increases with height, and there is stable air above the crest of the ridge with less stable air above that and a stable layer below the ridge. The formation of clouds on the lee-side may indicate turbulent flying conditions. Further information can be found in the ATSB website safety publications: Mountain wave turbulence.

Figure 2: Mountain wave turbulence

Figure 2: Mountain wave turbulence

Source: US Federal Aviation Administration

Flight crew harnesses

The aircraft’s flight crew seats are fitted with five point harnesses. The harness consists of a lap belt, a rotary buckle, a crotch strap, two shoulder straps and inertia-reel assembly with emergency locking retractors and cable control assembly (Figure 3). At the time of the turbulence, both flight crewmembers had the five points of their harnesses fitted, but with their shoulder harnesses in the AUTOMATIC position. In the AUTOMATIC position, the shoulder harness inertia-reel permits the occupant to move forward slowly, but locks when the straps are pulled at 1.5G and remains locked until the force is removed. In the MANUAL position, the shoulder straps are locked. The shoulder harness is primarily intended to mitigate forward movement of the torso and head.

The lap belt combined with the crotch strap are the primary means of restraint for turbulence encounters and exposure to negative-G forces. The crotch strap is also referred to as the ‘negative-G strap’ and its purpose is to reduce upward movement of the lap belt during negative-G aircraft motion. The length of the crotch strap should be adjusted such that no slack exists in the strap when the lap belt is properly positioned in the pelvic region. In this position, the crotch strap will resist the upward pull from the shoulder harness in negative-G.

When the aircraft encountered the negative-G turbulence, the captain felt the aircraft drop from underneath them and struck their head on the overhead air-vent and light. The captain and first officer reported that they had their lap belts tightened to ‘firm but comfortable’. The first officer reported that they may have hit their head on the ceiling of the flight deck, but received no injuries. The captain reported that some crotch straps do loosen during flight. The captain also advised that they had set their seat height so their eyes were lined up with height bar markers on the screen. They estimated that provided them with about 20-25 cm head clearance.

Figure 3: Aircraft flight crew harness

Figure 3: Aircraft flight crew harness

Source: Operator

Safety analysis

The flight crew had briefed and prepared the aircraft for flight in forecast severe turbulence.

As the aircraft tracked from waypoint HONEY to DALEY, it entered the lee-side of the Brindabella Ranges, tracking towards the north-east with a strong tailwind component. The wind was forecast to be 30 kt at 5,000 ft, increasing to 45 kt at 7,000 ft and within 30° of perpendicular to the ridgeline, at this location. Therefore, the abrupt encounter with turbulence was probably the result of mountain wave activity.

During the encounter, the flight crew described their movement relative to the aircraft as vertical when the aircraft dropped from underneath them. The primary method of restraint for negative-G is the lap belt supported by the crotch strap. If there is slack in the lap belt, this will permit the body to move up relative to the lap belt, and if there is slack in the crotch strap, this will permit the lap belt to move up if it is pulled upwards by the shoulder harness. The captain reported that the crotch strap can loosen with occupant movement and the aircraft was subject to minor fluctuations in G before the turbulence incident. Therefore, the captain’s injury was probably the result of some measure of slackness in their crotch strap.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The severe turbulence incident was probably an encounter with mountain wave activity in the lee-side of the Brindabella Ranges.
  • The captain was probably insufficiently restrained by their crotch strap to prevent them striking their head during the encounter with turbulence.
  • The flight crew were prepared for the risk of an encounter with severe turbulence during the descent and approach to Canberra.

Safety message

This incident highlights the importance of flight crew preparation for entry into an area of forecast turbulence and the importance of ensuring the correct adjustment of all harness straps. The captain planned to activate the seat belt sign early on the descent into Canberra and briefed the cabin crew accordingly. On descent into Canberra, all personnel were seated, the seat belt sign was activated and the aircraft speed reduced to turbulence penetration speed before the encounter with severe turbulence, which minimised the risk of injury to personnel and damage to the aircraft. However, despite the precautions taken by the crew, the captain received minor injuries.

Further information on flight crew harnesses can be found in United States Federal Aviation Administration Advisory Circular 21-34: Shoulder harness – safety belt installations.

Aviation Short Investigations Bulletin - Issue 56

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

__________

  1. Pilot Flying (PF) and Pilot Monitoring (PM): procedurally assigned roles with specifically assigned duties at specific stages of a flight. The PF does most of the flying, except in defined circumstances; such as planning for descent, approach and landing. The PM carries out support duties and monitors the PF’s actions and the aircraft’s flight path.
  2. Area forecast (ARFOR): routine forecasts for designated areas and amendments when prescribed criteria are satisfied. Australia is subdivided into a number of forecast areas.
  3. Significant meteorological information (SIGMET): a weather advisory service that provides the location, extent, expected movement and change in intensity of potentially hazardous (significant) or extreme meteorological conditions that are dangerous to most aircraft, such as thunderstorms or severe turbulence.
  4. Flight level: at altitudes above 10,000 ft in Australia, an aircraft’s height above mean sea level is referred to as a flight level (FL). FL 210 equates to 21,000 ft.
  5. G load: the nominal value for acceleration due to Earth gravity. In flight, g load represent the combined effects of flight manoeuvring loads and turbulence and can have a positive or negative value.
  6. This number varies between references with a lower limit of 15 kt and upper limit of 25 kt cited.

Occurrence summary

Investigation number AO-2016-132
Occurrence date 10/10/2016
Location 30 km south of Canberra Airport
State Australian Capital Territory
Report release date 17/01/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Turbulence/windshear/microburst
Occurrence class Serious Incident
Highest injury level Minor

Aircraft details

Manufacturer Bombardier Inc
Model DHC-8-402
Registration VH-LQM
Serial number 4450
Aircraft operator Sunstate Airlines
Sector Turboprop
Operation type Air Transport High Capacity
Departure point Melbourne, Victoria
Destination Canberra, Australian Capital Territory
Damage Nil

Taxiing collision involving Boeing 717, VH-NXN, and Fokker F28 MK 0100, VH-NHF, Paraburdoo Airport, Western Australia, on 5 October 2016

Final report

Report release date: 17/01/2017

What happened

On 5 October 2016, at about 1600 Western Standard Time (WST), a Boeing 717 (B717) aircraft, registered VH-NXN (NXN), was being operated by Cobham Aviation Services as QantasLink, on a scheduled passenger flight from Paraburdoo Airport to Perth, Western Australia. On board were the captain, first officer, three cabin crewmembers and 115 passengers.

The aircraft had been parked on Bay 2 facing south-west towards the terminal building, and the flight crew planned to depart from runway 24 (Figure 1). The captain commenced taxiing, turning the aircraft around to the right in accordance with the normal taxi procedure. As the aircraft turned, the captain sighted a company B717 aircraft about to land on runway 06. The captain quickly assessed that due to limited apron space at Paraburdoo, they needed to taxi behind a Network Aviation Fokker F28 MK 0100 (F100) aircraft, registered VH-NHF (NHF), which was parked on Bay 1, also facing the terminal, to allow the inbound B717 room to pass and taxi to Bay 2, which they had just vacated.

Figure 1: Paraburdoo Airport showing runways and parking bays

Figure 1: Paraburdoo Airport showing runways and parking bays

Source: Google earth and aircraft operator – annotated by ATSB

After starting a left turn to taxi behind the F100, the captain was not confident there was sufficient clearance between the two aircraft, and asked the first officer to request a member of ground staff to come out as a ‘wing walker’.

An engineer for Network Aviation, who had been working on the F100, observed NXN taxiing. As NXN deviated from the painted taxi line, the engineer became concerned about the proximity of its left wingtip to the tail of the parked F100. As a result, as NXN taxied forward, the engineer checked the clearance between its wingtip and tail of the F100, and gave the captain the ‘thumbs up’ signal to indicate the aircraft was clear.[1] The captain assumed therefore that the aircraft was clear and continued taxiing around the back of the F100, then turned the aircraft sharply around to the right (Figure 1 insert). The aim was to leave enough room for the inbound B717 to taxi past, and then continue onto the taxiway once they were clear.

The engineer had expected NXN to taxi towards the runway rather than turning around the back of the F100. The engineer immediately assessed that the horizontal stabilisers of the two aircraft may collide, and tried to signal the captain to stop, but was near the wing of the aircraft and no longer in the captain’s sight. The engineer ran towards the front of the aircraft and waved to the captain to stop. The captain braked heavily. The crew did not feel a collision. Some hours later, it was determined that the horizontal stabiliser of NXN had slid under that of NHF, scraping the surface, and both aircraft sustained minor damage (Figure 2). The passengers and crew of NXN were not injured and no one was on board NHF.

Figure 2: Horizontal stabiliser of NXN under that of NHF

Figure 2: Horizontal stabiliser of NXN under that of NHF

Source: Cobham Aviation Services

Airport facilities

Paraburdoo Airport had one taxiway from the runway to the apron area. There were three parking bays, but only two were suitable for F100 and B717 aircraft. Bay 1 was occupied by the F100, NHF, and NXN had been parked on Bay 2. It was also not possible for a B717 to turn around on the runway except at the thresholds due to pavement restrictions.

Captain comments

Awareness of inbound aircraft

NXN was a few minutes late for their scheduled departure and the inbound B717 arrived several minutes earlier than scheduled. There was no procedure for the aircraft operator to notify pilots of the potential for multiple aircraft (from that company) to be at Paraburdoo at the same time.

The captain (and first officer) of NXN reported that they did not hear the inbound or final calls from the crew of the inbound B717. This may have been because at about the time of the inbound calls, the crew of NXN were resolving loadsheet issues with ground staff.

The captain commented that the ground staff were busy due to the arriving B717, and did not alert the crew of NXN to its imminent arrival. Furthermore, a wing walker was not at the parking bay when NXN started taxiing, which was the normal procedure.

The crew of NXN reported that they were not aware of the arriving B717 until they commenced taxiing. While the inbound aircraft had landed on runway 06, the conditions necessitated a departure from runway 24 for NXN.

Non-normal taxi manoeuvre

The captain reported that they would normally conduct a right turn out of the parking bay and taxi the aircraft directly onto the taxiway leading to the runway. This was what the crew were expecting to do until they sighted the inbound B717, landing in the opposite direction to their planned take-off direction.

When the captain of NXN saw the other B717 about to land on runway 06, they thought they were going to be ‘boxed in’ and formulated a plan in ‘about 10 seconds’ for the two B717s to pass on the apron area. The captain needed to formulate a plan with limited time available due to parking space constraints and noting that B717-size aircraft could only conduct 180° turns at the runway thresholds. The captain assessed that the only way they could pass the incoming B717 was to taxi behind the parked F100.

The captain later realised that they could have taxied to the runway 06 threshold, turned there, and taxied back to the runway 24 threshold, but that would have added about 2 km to their taxi and therefore increased fuel required.

Engineer comments

The engineer gave the ‘thumbs up’ having assessed that the wingtip of NXN would not collide with the (tail of the) F100, but did not expect the captain to continue taxiing around the parked aircraft. The engineer was only trying to ensure the aircraft did not collide having assessed the potential for a collision. They had not intended to act as a ‘wing walker’, did not know what the captain’s intentions were, and had no means of communicating with the captain other than by hand signals.

By the time the engineer assessed that there was insufficient clearance between the horizontal stabilisers of the two aircraft, they were no longer in sight of the captain. The horizontal stabiliser of NXN slid under that of the F100 before the engineer was able to signal the captain to stop.

Ground crew resources

The flight crew could not visually confirm the relative position of the two aircraft due to the limited view from the flight deck. Ground handling agent staff would normally have been available to assist the crew, but their attention had shifted to management of the inbound company aircraft. The first officer was about to request a wing walker from the ground staff, when the engineer appeared and signalled the captain.

The crew would have considered the use of ground vehicles if they had been available, but there was no infrastructure such as a tug or tow bar available at Paraburdoo.

Safety analysis

Due to the inbound aircraft and tarmac constraints, the flight crew assessed that a non-standard taxi manoeuvre was necessary to allow the two B717 aircraft to pass.

There was no wing walker in position on the tarmac to provide the crew with a more timely warning of the proximity of the tail to the tail of the F100, and with whom the crew could communicate to discuss their intentions. The crew were about to request a wing walker because the captain was not certain they would be clear of the F100, when the engineer from another company appeared.

Although the engineer used a standard hand signal, the crew interpreted the ‘thumbs up’ to mean that both the wing tip and tail were clear. The crew had not communicated with the engineer until the engineer gave the signal.

The engineer did not anticipate the sharp right turn of the aircraft after it had apparently passed the F100. The engineer was not in a position to warn the crew about the position of the tail once the sharp right turn had commenced.

Findings

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

  • The crew was unaware of the inbound company B717 until after taxi had commenced, then taxied on a non-standard path to accommodate entry of that aircraft onto the tarmac.
  • A ground handling agent wing walker was not in place to assist the crew as they taxied.
  • The inability to communicate verbally with the non-company engineer resulted in the crew interpreting the engineer’s thumbs up signal as meaning the entire aircraft was clear of the parked aircraft.

Aviation Short Investigations Bulletin - Issue 56

About this report

Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2017

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

__________

  1. The NXN company operations manual stated that the thumbs up signal means you are clear to proceed.

Occurrence summary

Investigation number AO-2016-129
Occurrence date 05/10/2016
Location Paraburdoo Airport
State Western Australia
Report release date 17/01/2017
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Taxiing collision/near collision
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 717-200
Registration VH-NXN
Serial number 55095
Aircraft operator National Jet Systems
Sector Jet
Operation type Air Transport High Capacity
Departure point Paraburdoo, Western Australia
Damage Minor

Aircraft details

Manufacturer Fokker B.V.
Model F28 MK 0100
Registration VH-NHF
Serial number 11458
Aircraft operator Network Aviation
Sector Jet
Operation type Air Transport High Capacity
Damage Minor