On 6 February 2017 at around 0730 Australian Eastern Daylight-saving Time (AEDT), the pilot of a Cessna 210 aircraft, registered VH-HZE, departed Mildura Airport, Victoria, for Broken Hill Airport, New South Wales (NSW), to conduct a private business flight under visual flight rules.[1]
The pilot had been to the airport the previous afternoon to prepare the aircraft, which included filling the two fuel tanks.
After arriving in Broken Hill an hour after departure, the pilot was joined by two work colleagues. From Broken Hill, they flew for 40 minutes to Katalpa Station, NSW, to visit clients. After Katalpa, they flew 30 minutes to Pine View Station, NSW, to visit other clients. From Pine View Station, the pilot flew 45 minutes back to Broken Hill to drop off their two work colleagues. After departing Broken Hill, the pilot tuned the radio to Mildura aerodrome weather information service (AWIS) to check the weather. The weather was cloudy, but suitable for a visual approach.
Approximately 70 NM (130 km) from Mildura, the pilot listened to the AWIS again. The AWIS advised that there was broken[2] cloud at Mildura at 4,000 ft and visibility was 10 km.
Passing 12 NM (22 km) on approach to Mildura, the pilot made a broadcast to advise that they were approaching the airport. The pilot reported that during the approach, the AWIS indicated that the cloud base was varying between 1,000 ft and 3,000 ft. Therefore, the pilot decided to approach Mildura overhead to observe the conditions.
Approaching the airport, the pilot noticed the weather was overcast over the airport, but clear on the northern side of the Murray River.
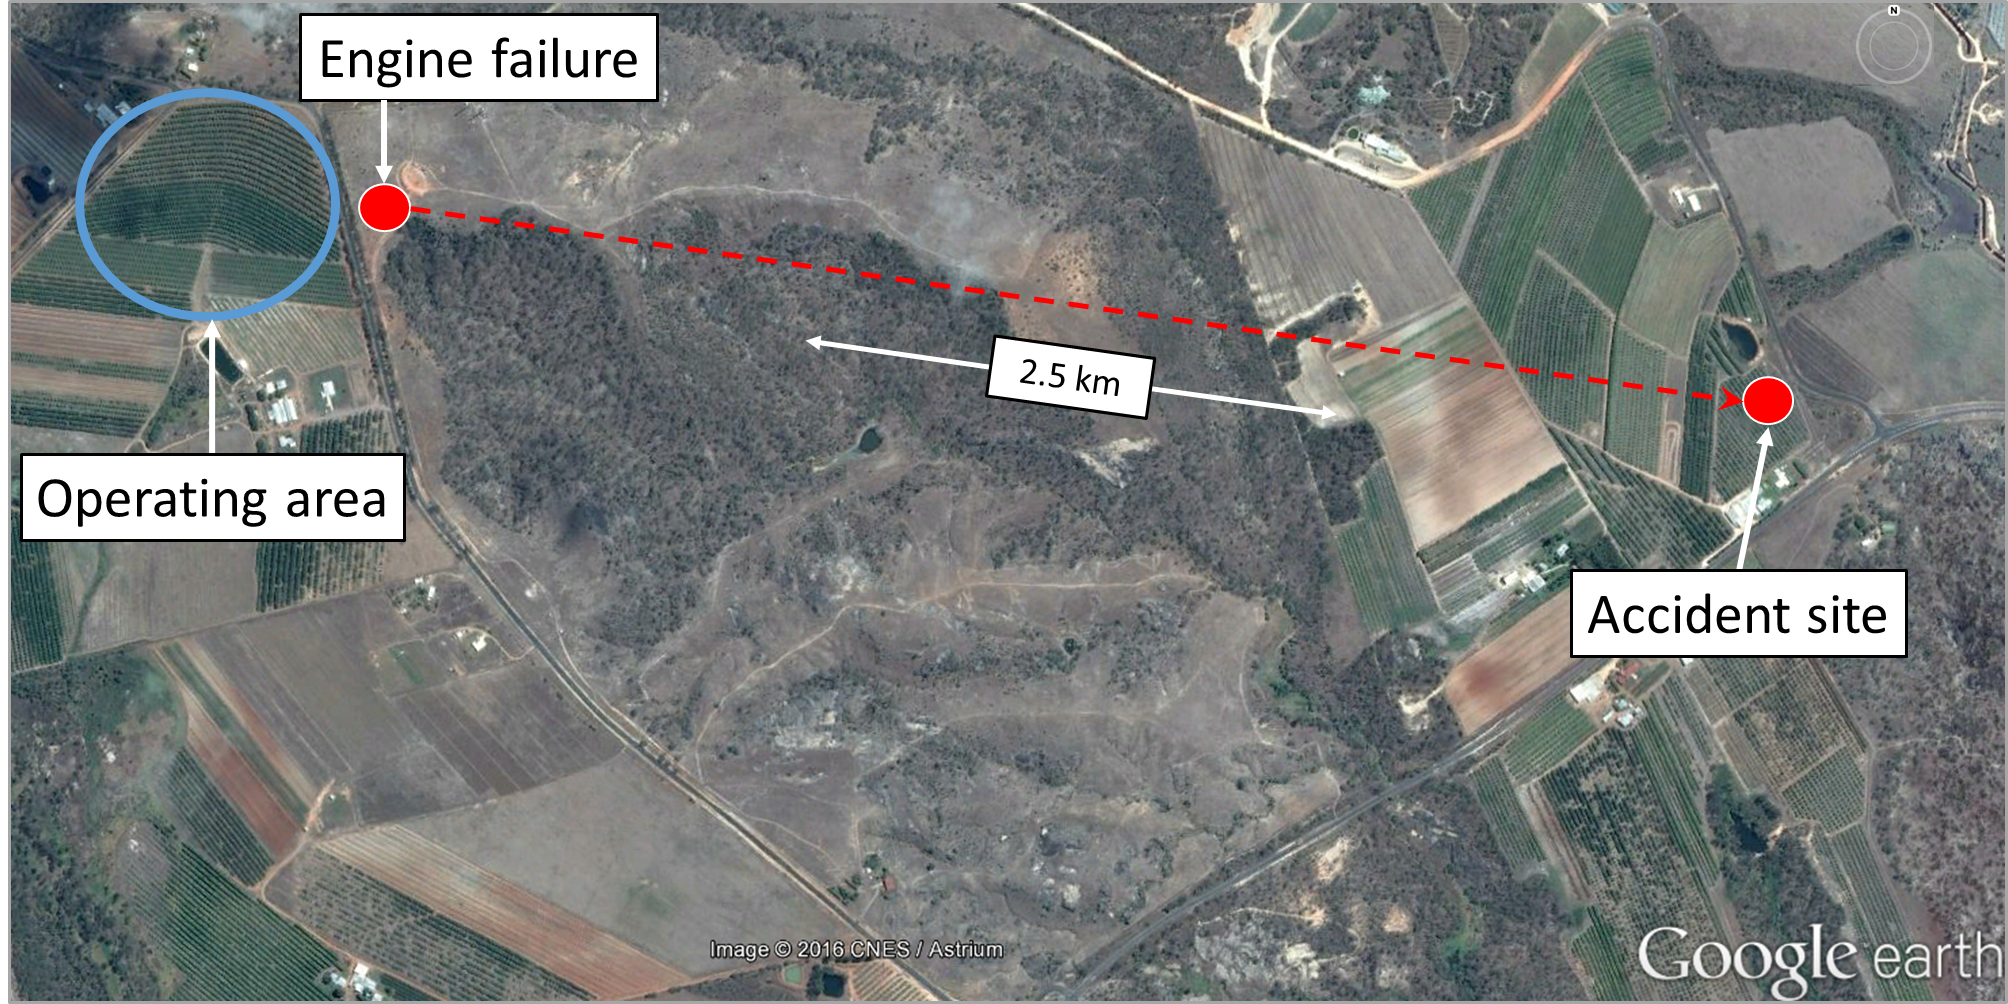
The pilot manoeuvred the aircraft initially to the east and then to the north of Mildura for about 20 minutes before they set up for a straight-in approach for runway 18. Once established on the approach, they started descending. They were about to make a broadcast that they were joining a straight-in approach to runway 18 when the engine stopped. The pilot then made a MAYDAY[3] call to Melbourne Centre.
The pilot had been flying the aircraft with the fuel tank selector set to both tanks. They cycled the selector to the right tank and switched on the auxiliary fuel pump, but there was no response from the engine. The pilot noticed that their fuel flow computer was indicating 90 L of fuel remaining when the engine failed.
The pilot decided not to attempt to land on the runway as they would have had to fly over a populated area and instead identified Amaroo Road as suitable for a forced landing. On approach, they noticed there were powerlines on both sides of the road and changed their landing site to a nearby paddock.
The pilot landed the aircraft in the paddock and collided with a fence during the ground roll. Once the aircraft had stopped, the pilot selected the master switch to off and exited the aircraft uninjured. The aircraft was substantially damaged (Figure 1).
Figure 1: Damage to HZE
Source: Pilot
Pilot comments
The pilot provided the following comments:
At most, the trip would take 4 to 4.5 hours, so fuel was not expected to be an issue.
The fuel selector was selected to both tanks.
There were no abnormal engine indications or sounds from the engine to indicate that the engine was about to fail.
Fuel management
The pilot reported they filled the tanks with around 197 L the evening before. This was consistent with the amount of fuel they believed was used from the last flight, around 200 L. Overall, after refuelling, the total amount of useable fuel on board should have been 435 L. Their planned fuel flow was about 75 L per hour. Therefore, their planned endurance with full fuel tanks was just under six hours. The pilot recorded they were flying for four hours and 15 minutes before the engine failed.
The pilot reported that the aircraft was parked with the left wing low at the fuel point and when they refuelled the fuel tanks in the wings, so they might have stopped before the tanks were full. However, the pilot reported that the fuel gauges indicated the tanks were about full. The pilot advised that they visually checked the fuel levels the next morning but did not use a dipstick. The fuel caps are on the wing tips which makes visually checking the fuel level difficult.
The aircraft was installed with a fuel flow computer known as an EDM 930 (also known as a JPI). The fuel flow computer tracks the fuel flow to the engine to calculate fuel remaining. The pilot must enter the fuel on board the aircraft at the start of the flight, as the computer does not take fuel measurements from the fuel tanks.
After the engine is started, there is a prompt on the computer to enter whether any fuel was added to the aircraft. If no fuel is added to the tank, the user can exit the screen, otherwise they can choose ‘next’ to select ‘yes’ if fuel was added which automatically resets to a quantity of 435 L.
Upon approach, the fuel gauge indicated the left tank was near empty, but the right was half full.
The Cessna fuel system is designed so fuel can be drawn from either the right tank or the left tank or from both tanks at the same time. The pilot advised that they normally flew with the fuel selector on both tanks. They advised that during the cruise at 4,000 ft, they had leaned the fuel mixture.
After the accident, an inspection was conducted which found the left fuel tank was empty and the right tank had 25 L of fuel remaining, half of which was useable. The Cessna 210 manual states that if the aircraft is flown out-of-balance when fuel tanks contents are one quarter full or less, then the fuel tank outlets can uncover, causing fuel starvation and engine stoppage. The fuel selector was selected on ‘right tank’, but the pilot had advised that this was selected after the engine had failed.
Weather
The Bureau of Meteorology provided a weather report with the aerodrome forecasts.
The amended aerodrome forecast (TAF)[4] which was valid at the time of the accident was broken clouds at 1,500 ft, with rain and visibility was greater than 10 km. It also forecast intermittent periods of broken cloud at 600 ft with visibility of 5,000 m with rain. These conditions were still suitable for a visual flight.
Previous occurrences
A search of the ATSB’s database found 12 occurrences in 2016 where fuel starvation led to an engine failure. Two examples are:
On 18 April 2016, a Lancair ES aircraft took off from an airstrip near Mansfield, Vic. and was climbing to about 500 ft when the engine lost power (ATSB investigation AO-2016-037[5]). The pilot established the aircraft in a glide and conducted a forced landing. The maintenance personnel assessed the reason for the power loss was fuel starvation as the aircraft was parked on an incline prior to taxi and fuel may have drained away.
On 12 August 2016, the pilot of a Cessna 172 was conducting powerline inspections near White Cliffs, NSW (ATSB occurrence 201602162). After finishing checking a powerline, the engine lost power and the pilot conducted a forced landing. The engineering inspection revealed the engine failed due to a lack of useable fuel in the left fuel tank.
Safety analysis
The pilot thought the aircraft had been filled to the maximum fuel level because they had considered how much the fuel was used the previous flight, which was 200 L, and the tanks did not appear to take more fuel at 197 L. The ground where the aircraft was refuelled was on an incline which meant the aircraft had its left wing down, so the left tank may have appeared full before it actually was, as the refuelling points are on the end of the wing. The aircraft was parked on level ground overnight, to ensure fuel did not leak out through the breather. The following morning, the fuel was checked visually in the tank, but not physically by using a dipstick. Therefore, it is uncertain whether the aircraft was filled with the maximum fuel level.
The pilot was using the fuel flow computer for fuel usage monitoring, however, it does not provide a direct reading of fuel contents from the fuel tanks, only fuel flow. The fuel remaining is calculated by the computer by subtracting the fuel consumed in-flight from the fuel manually entered by the pilot at the start of the flight. Only the fuel gauges provide the pilot with an indication of the actual amount of fuel left on board.
While circling Mildura Airport attempting to find a break in the clouds to land, the pilot conducted numerous turns with both fuel tanks were selected. However, as the left tank was likely to be empty at that time, it is probable the right fuel tank outlet was uncovered during the manoeuvring, resulting in fuel starvation and subsequent engine failure.
Given the fuel burn rate and the remaining usable fuel on board, the aircraft had about 10 minutes of flying time remaining before complete fuel exhaustion.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The engine failed due to fuel starvation when the limited amount of fuel remaining in only one of the two tanks became unusable during manoeuvring.
Prior to departure, the aircraft’s fuel tanks were probably not full. However, the pilot selected full fuel tanks on the fuel flow computer and therefore the fuel flow computer provided the pilot with a higher reading of fuel on board than what was actually on board.
Safety message
The investigation is a reminder of the importance of monitoring fuel levels prior to – and during – the flight. When monitoring the fuel levels, it is important to note the limitations of flight instruments. The ATSB has published a report Avoidable Accidents No. 5 - Starved and exhausted: Fuel management aviation accidents which outlines strategies in fuel management.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 26 January 2017, a Network Aviation Fokker F28, registered VH-NHZ (NHZ), conducted a flight from Perth Airport, Western Australia (WA), to Newman Airport, WA. On board the flight were two flight crew, three cabin crew and 31 passengers.
The aircraft was initially pushed back from the parking bay at about 1600 Western Standard Time (WST), for the Perth-Newman-Perth service. However, another company aircraft, scheduled to operate the Perth-Karratha-Perth service, became unserviceable and the company elected to return NHZ to the gate and reschedule NHZ to operate a Perth-Newman-Karratha-Perth service. This required the flight crew to re-plan the flight while ground staff transferred passengers and baggage from the unserviceable aircraft to NHZ. In addition to the transfer of passengers and baggage from the Perth-Karratha service, there were 30 bags, which had been offloaded from another Perth-Karratha service due to weight restrictions, which were planned to be loaded on board NHZ for the rescheduled service.
During the flight planning process, the flight crew were presented with an amended load instruction sheet (LIS) and two customer management (CM) summaries. The LIS indicated the number of bags to be loaded and the distribution of the load between the baggage compartments. The CM summaries were produced by the passenger check-in system and provided the total passenger number and distribution of passengers, along with the total number of bags and their weight.
The LIS indicated there were 28 bags to be loaded in compartment A and 30 bags to be loaded in compartment B, for a total of 58 bags. The first CM summary, annotated as ‘Acceptance not finalised’, indicated there were 34 passengers with 30 bags at a total weight for the bags of 388 kg. The second (final) CM summary indicated there were 31 passengers with 28 bags at a total weight for the bags of 365 kg.
The flight crew entered 58 bags with a total weight of 388 kg (correct number of bags, but 365 kg less than the actual weight) and 31 passengers (the correct number of passengers) into their electronic load sheet for departure. The flight departed Perth and landed at Newman without incident. After arrival at Newman, the ground staff informed the flight crew that the actual baggage weight appeared to be greater than what they expected. The Newman ground staff weighed the baggage, which was found to be 755 kg (planned load 388 + 365 = 753). The flight crew worked with the Newman ground staff to resolve the discrepancy and the flight continued to Karratha and Perth without further incident.
Check-in system
According to the operator, there was some difficulty getting the paperwork to the flight crew when the flight was re-scheduled to include the Karratha service. At the time the decision was made to amalgamate the services, the check-in system had recorded that the services to both Newman and Karratha had departed. The first CM summary, annotated ‘Acceptance not finalised’ with boarding time 1725, was delivered to the flight crew by the gate staff for the purpose of planning their flight. When the flight closed, the final CM summary with boarding time 1820 was generated from check-in and then delivered to the flight crew with the passenger manifest. The flight crew then crosschecked the final CM summary with the figures entered into the electronic load sheet (see electronic load sheet) and the completed LIS.
Each CM summary delivered to the flight crew supersedes any previous CM summary. The second CM summary was the final CM summary and had the correct number of passengers. However, both CM summaries had incorrect baggage data. The operator considered it possible that the attempt to amalgamate the services, which were both recorded as departed in the check-in system, resulted in incorrect baggage data on the final CM summary. The final CM summary had the correct number of passengers and their baggage, but did not take into account the extra bags, which had been off-loaded from the earlier flight.
Electronic load sheet
The flight crew had electronic flight bags (iPads), which were used to produce the electronic load sheet from the data provided from the LIS and CM summary.[1] The electronic load sheet was produced with the total number of bags in accordance with the LIS, the baggage weight of 388 kg in accordance with the first CM summary marked ‘Acceptance not finalised’ and the number and distribution of passengers in accordance with the final CM summary.
Flight crew comments
The captain reported that they performed a crosscheck of the paperwork and that they commented to the first officer that they needed to be extra careful due to the number of changes that were occurring during the process of re-planning the flight.
Safety analysis
During the flight planning process, the crew received several items of paperwork for the re-schedule of the service to include Karratha. It is likely that the first CM summary contained the 30 bags offloaded from an earlier flight. The final CM summary received by the flight crew contained incorrect information on the total number and weight of bags loaded in the aircraft, but was in accordance with the passengers’ checked-in baggage.
It is likely that when entering the information into the electronic load sheet, the crew entered the baggage weight from the CM summary annotated ‘Acceptance not finalised’ during the planning stage. It is likely that the crosscheck of baggage weight entered into the electronic load sheet from the first CM summary (388 kg) with a final CM summary (365 kg) resulted in an incorrect assumption that the planned baggage weight was acceptable in the mind of the captain.
While the LIS has the total number of bags and their distribution between the cargo compartments, it does not include the weight of baggage. Hence, the LIS may be used for entering and crosschecking baggage numbers, but it cannot be used for entering or crosschecking baggage weight. It is probable that the flight crew did not crosscheck the total number of bags on the LIS against the final CM summary.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The final CM summary provided to the flight crew contained incorrect baggage data, which was possibly the result of an attempt to amalgamate two services already recorded in the check-in system as departed, and did not include the extra baggage, which was previously offloaded from an earlier Perth-Karratha service.
It is probable that when completing the electronic load sheet, the flight crew entered the total number of bags from the LIS and the baggage weight from the CM summary annotated ‘Acceptance not finalised’. This weight was probably checked against the final CM summary and considered acceptable in the mind of the flight crew.
The total number of bags on the LIS was probably not crosschecked with the final CM summary, resulting in the crew not detecting the error and the aircraft departing with the incorrect weight and balance calculations.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they are taking the following safety action:
Advisory bulletin
The operator issued an advisory bulletin to communicate to their staff the aircraft loading system requirements, including the interface requirements between departments for aircraft dispatch. This includes the point that the baggage crosscheck is the final CM summary number of bags versus number of bags on the LIS.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 25 January 2017, a Jetstar Airways Airbus A320-232, registered VH-VGJ (VGJ), taxied for a scheduled passenger transport flight from Newcastle (Williamtown) Airport, New South Wales, to Brisbane Airport, Queensland. There were six crewmembers and 165 passengers on board the aircraft. The captain was the pilot monitoring and the first officer was the pilot flying.[1]
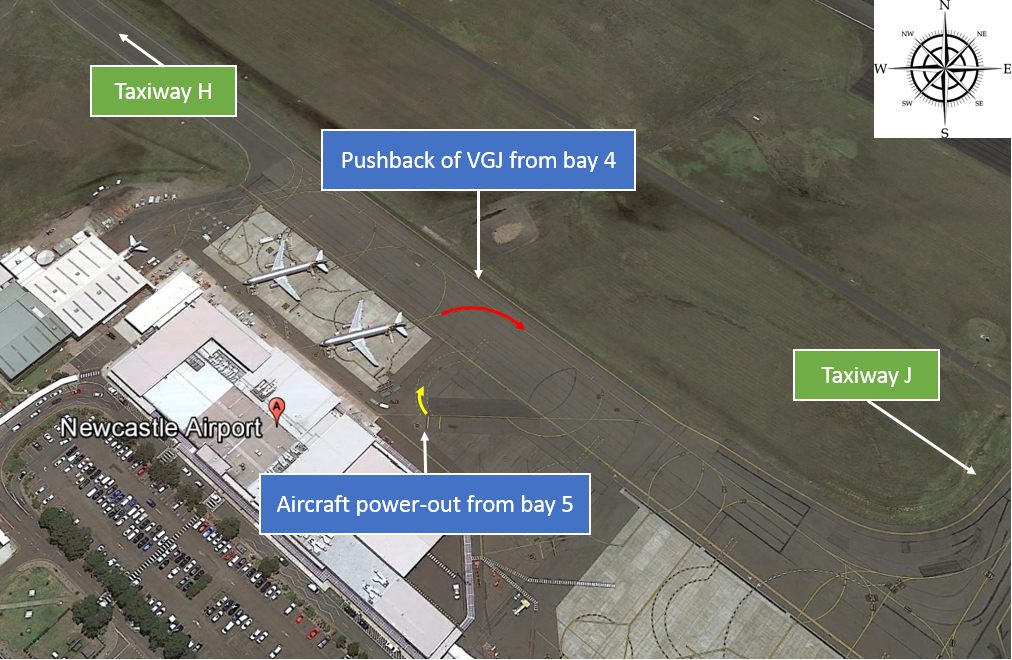
The aircraft parked at bay 4 at the Newcastle Airport terminal for passenger disembarkation and boarding (Figure 1). Bay 4 was a ‘pushback’ bay, which means that when the aircraft is ready for departure, the aircraft is pushed backwards from the parking bay by a tug under the supervision of a dispatcher. Another operator’s aircraft was parked on bay 5, to the left of VGJ. Bay 5 was a ‘power-out’ bay which means that on departure, aircraft taxi from the bay under their own power by turning sharply away from the terminal.
At about 1836 Eastern Daylight-savings Time (EDT), the crew of VGJ received a clearance from the surface movement controller to pushback, which placed VGJ to the right rear quarter of the aircraft parked on bay 5, and facing towards taxiway H (Figure 1). The dispatcher was walking beside the aircraft and was connected to the nose of VGJ by a headset for communications with the flight crew. The flight crew started the engines during the pushback in accordance with standard procedures. After the pushback was completed, the flight crew set the brakes, the tug disconnected and the dispatcher removed the nose wheel steering pin. [2] The flight crew then started their ‘after start flows’ (see: After start flows). After the tug disconnected from VGJ, the tug driver moved it to a position adjacent to the left wingtip of VGJ, facing towards the aircraft on bay 5.
At about 1838, the crew of the aircraft on bay 5 requested a clearance to taxi for departure. The surface movement controller questioned whether the aircraft could taxi to taxiway J and avoid VGJ.[3] The flight crew responded that they could. At this stage, the flight crew on board VGJ interrupted their ‘after start flows’ to monitor the other aircraft. The captain, seated in the left seat of VGJ, did not believe there was sufficient clearance for the other aircraft to turn around for taxiway J without a collision. The aircraft started to taxi from bay 5 in a right power-out turn, but stopped within a few metres.
When the tug driver observed the aircraft on bay 5 move towards them,[4] they moved the tug away from VGJ over to the terminal side of the apron, near bay 4, to remain clear of the other aircraft. Meanwhile the dispatcher assisting the aircraft on bay 5, had also moved from bay 5 towards bay 4 in order to monitor and signal wingtip clearance for the left wing of the aircraft conducting the power-out from bay 5.
Figure 1: Newcastle Airport apron
Source: Google earth, annotated by ATSB
Radio communications continued between air traffic control and the aircraft departing from bay 5, until it was confirmed that the aircraft would wait for VGJ before taxiing any further. The captain of VGJ, who was looking out the left window of the flight deck towards the bay 5 aircraft and the terminal, sighted their tug and a dispatcher near bay 4. They assumed that the dispatcher near bay 4 was their dispatcher, who had disconnected from their aircraft while they were monitoring the bay 5 aircraft movements and radio communications. At about 1840, the flight crew on board VGJ requested and received a clearance to taxi for runway 12 via taxiway H. The flight crew selected their taxi lights on, released the brakes and increased power.
The dispatcher for VGJ was still connected to the aircraft nose with their headset and waiting for their clearance from the flight crew to disconnect. They observed the taxi lights for VGJ illuminate, then they heard the engine noise increase, and then the aircraft started to taxi. They immediately disconnected their headset from the aircraft and moved clear to the left of the aircraft towards the terminal with the headset and the nose wheel steering pin. Once the dispatcher was clear of the aircraft, they turned around to display the nose wheel steering pin to the flight crew, but the captain was not looking towards them.
After start flows
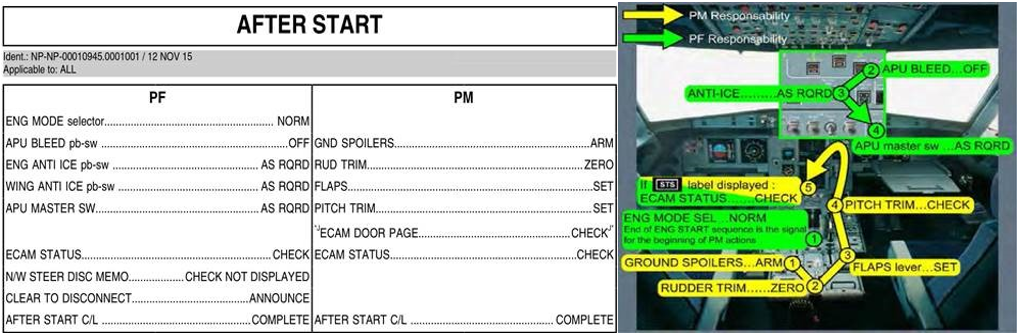
On completion of starting both engines, the flight crew conduct their ‘after start flows’, which are memory item checks split between the pilot flying and pilot monitoring (Figure 2). The second-to-last item for the pilot flying is the announcement to the dispatcher that they are clear to disconnect. After the dispatcher disconnects their headset from the aircraft, they walk clear of the aircraft and provide a ‘thumbs-up’ signal to the flight crew while holding up the nose wheel steering pin for the flight crew to sight. During the ‘after start flows’, the attention of the flight crew on board VGJ was diverted to the radio communications between the aircraft parked on bay 5 and the surface movement controller.
Figure 2: After start flows
Source: Operator
The last item on the ‘after start flows’ is for the flight crew to complete the challenge and response ‘after start checklist’, which is as follows:
ANTI ICE…AS RQRD
ECAM STATUS…CHECKED
PITCH TRIM…SET
RUDDER TRIM…ZERO
DISP CLRNCE…SIGHTED
The last item on the ‘after start checklist’ is confirmation that the dispatcher was sighted clear of the aircraft. The left seat or right seat pilot reports to the other pilot ‘dispatch clearance sighted’. In this serious incident, the terminal was on the left side of VGJ and therefore it was expected that the captain, in the left seat, would sight the dispatcher. The captain reported remembering sighting a dispatcher, but could not recall what was communicated on the flight deck between the flight crewmembers.
On completion of the ‘after start checklist’, the flight crew request taxi clearance and turn on the taxi light.
Tug movements
After the tug disconnected from the aircraft, the tug driver moved the tug clear of the aircraft and initially waited for the dispatcher near the left wingtip. The tug normally waited beside the aircraft to offer the dispatcher a lift and because the nose wheel steering pin is stowed in the tug when removed from the aircraft. However, when the bay 5 aircraft started to move, the tug moved from the left wingtip to the terminal building near parking bay 4.
Safety analysis
After VGJ was pushed-back from bay 4 and the flight crew had started their ‘after start flows’, their attention was diverted to a potential risk of collision associated with the taxi instructions and movement of an aircraft parked on bay 5. Following confirmation between the conflict aircraft and surface movement control that they would wait for VGJ, the captain of VGJ misidentified the dispatcher for the bay 5 aircraft as their own dispatcher. At this time, the tug, which would normally wait beside the departing aircraft for the dispatcher, had moved away from VGJ towards the terminal to avoid a conflict with the bay 5 aircraft. Therefore, the dispatcher sighted by the captain, was next to the tug used for the pushback of VGJ. This potentially provided an association between the tug and the dispatcher in the mind of the captain, who assumed the dispatcher had removed the nose wheel steering pin and moved away from the aircraft. The diversion of the flight crew’s attention away from their ‘after start flows’ probably resulted in the pilot flying not completing their memory items. This was not detected in the ‘after start checklist’ because the captain had misidentified the dispatcher for the bay 5 aircraft as the dispatcher for VGJ. Consequently, the dispatcher connected to VGJ was not cleared to disconnect prior to VGJ starting to taxi.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The flight crew on board VGJ were distracted during their ‘after start flows’ by the radio communications between an aircraft parked on bay 5 and surface movement control, and the subsequent movement of that aircraft which had a potential risk of collision with VGJ.
The captain on board VGJ misidentified the dispatcher for the bay 5 aircraft as their own dispatcher, which resulted in VGJ starting to taxi without clearing the dispatcher to disconnect.
Safety message
Following this serious incident the captain reported that their most important lesson was distraction management. They considered either slowing down the ‘after start flows’ or re-starting the ‘flows’, before the ‘after start checklist’, as the most practical risk mitigation strategies.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
During the afternoon of 29 January 2017, the deck crewmembers of Shanghai Spirit were conducting painting and routine touch-up work in the cargo holds. They used a mobile scaffold tower to access areas of bulkhead about 6 to 9 m above the hold bottom. Two crewmembers conducted the work from the upper tiers of the scaffold tower and remained unsecured on it when it was moved.
To access the full length of the hold bulkhead, the work required repositioning the scaffold tower on multiple occasions. After the work on the aft bulkhead was completed, it was decided to paint the hopper tank edge. As the scaffold tower was moved with the unsecured crewmembers, it became unbalanced and toppled forward onto the deck.
The two crewmembers on the scaffold tower were seriously injured in the fall and were evacuated to a hospital ashore for treatment.
What the ATSB found
The ATSB found that, contrary to established procedures, two crewmembers remained on the unsecured scaffold tower in preparation for repositioning, rendering it top-heavy and unstable. Consequently, when moved it toppled and fell. Additionally, neither crewmember on the scaffold tower utilised the required safety harness and associated safety lines which would have prevented them falling when climbing or working on the tower.
Finally, the afternoon work in hold number four was not supervised by an officer as required by company procedure and in contrast to the morning activity. The absence of formal supervision, in combination with a desire to expedite the task in difficult working conditions, probably led to the crewmembers remaining unsecured on the scaffolding as it was repositioned.
What's been done as a result
The scaffolding equipment operating instructions and maintenance manuals/guidelines have been included in the company’s safety management system. Further, there is now a requirement for monthly and quarterly inspection of the equipment.
The use of scaffolding is now specifically classed as ‘working at heights’ and is therefore subject to all planning and precautionary measures such as risk assessment, working aloft permits and precautions.
Personnel Protective Equipment training and awareness has been reviewed and enhanced. Additionally, new crewmembers will be subject to pre-joining training that now includes the use of scaffolding.
Safety message
This accident highlights the importance of adhering to procedures that assure safety as well as the value of effective supervision. Owners, operators and crewmembers are reminded to plan and undertake risk assessments for assigned tasks in order to identify any shortcomings in procedures and required risk-mitigation measures.
The occurrence
At 0824 Eastern Standard Time[1] on 27 January 2017, the 140 m geared bulk carrier[2]Shanghai Spirit (Figure 1), anchored in Keppel Bay, about 15 nautical miles[3] north-east of Port Alma, Queensland. The ship had just completed a voyage from Subic Bay, Philippines with a cargo of containers, and was expected to berth at Port Alma during the morning of 30 January 2017.
Figure 1: Shanghai Spirit alongside at Port Alma
Source: ATSB
While at anchor, the ship’s crewmembers went about routine duties including berthing preparations, repairs and maintenance. The following day, Saturday, was Chinese New Year and the ship’s crewmembers maintained only essential duties, opting to work on the Sunday.
On Sunday 29 January, during the chief mate’s morning watch, he discussed the day’s work with the master. This included painting and routine touch-up work in cargo holds (hold) number one and number four. Shortly after 0800, the chief mate briefed the bosun about the day’s work. He instructed the bosun to prepare mooring lines for the next day’s berthing, and then complete routine paint work in the holds. This required crewmembers to work from the ship’s portable, modular scaffold tower.
At about 0830, a work group consisting of the chief mate, the bosun, two able seamen (AB2 and AB3), the ordinary seaman (OS), and the deck cadet (cadet), commenced work in number one hold. They gathered the necessary equipment on the tank top in the hold. This included the ship’s scaffold tower, spray painting apparatus, harnesses and safety and securing lines. Their task was to touch up and paint sections of the hold’s aft bulkhead and topside tank, about 6 to 9 m above the tank top.
The crewmembers assembled five sections of scaffolding to allow access to an area of the bulkhead up to about 9 m above the tank top. The scaffold tower was secured by two guy ropes that had been run up out of the hold, and secured on deck. The chief mate, as the supervisor, oversaw the work from the tank top, and the bosun and AB3 painted from the scaffold tower. Both crewmembers wore safety harnesses with the safety lines leading up on to, and secured on the ship’s deck. The remaining crewmembers (AB2, OS and cadet) assisted with the paint preparations, moving equipment, and handling of the security and safety lines.
As each area of work was completed, the scaffold tower needed to be repositioned to access the next area. To do this, the bosun and AB3’s safety lines were released and they climbed down from the scaffold tower. Then the scaffold tower securing lines were released and the scaffold tower was repositioned and resecured. The bosun and AB3 then climbed up the scaffold tower, and with their safety lines resecured, recommenced work.
This process was followed throughout the morning. By 1130, the touch-up work in hold number one had been completed. The scaffold tower was disassembled and, along with the other equipment, moved to hold number four ready for work there after lunch.
At midday, the bridge watch duty changed over and the 1200-1600 bridge team consisting of the second mate assisted by AB2 commenced duty on the bridge. AB1 replaced AB2 in the deck work crew. The chief mate did not return to the deck in the afternoon as he rested in preparation for taking the bridge watch at 1600.
At about 1300, the team now consisting of the bosun, AB1, AB3, the cadet and the OS, went to hold number four. The scaffold tower was assembled (Figure 2) and the associated equipment prepared. As before, the bosun and AB3 painted from the scaffold tower and the remaining crewmembers (AB1, OS and cadet) assisted. The task commenced in the port aft corner of the hold.
Figure 2: Hold number four showing scaffold tower moves from port to starboard and positions of crewmembers on the tower viewed from forward
Source: ATSB
A similar work sequence of operation to that in hold number one was followed. However, when the scaffold tower was moved, the bosun decided that he and AB3 would not climb down. Instead, they remained on the scaffold tower as the OS and cadet repositioned it. Additionally, and in contrast with the morning’s activity, neither the bosun or AB3 wore safety harnesses and safety lines were not used.
The work progressed from port to starboard across the aft of the hold. The tower was moved in that direction, in line with the major axis of the scaffold tower footprint, about five times.
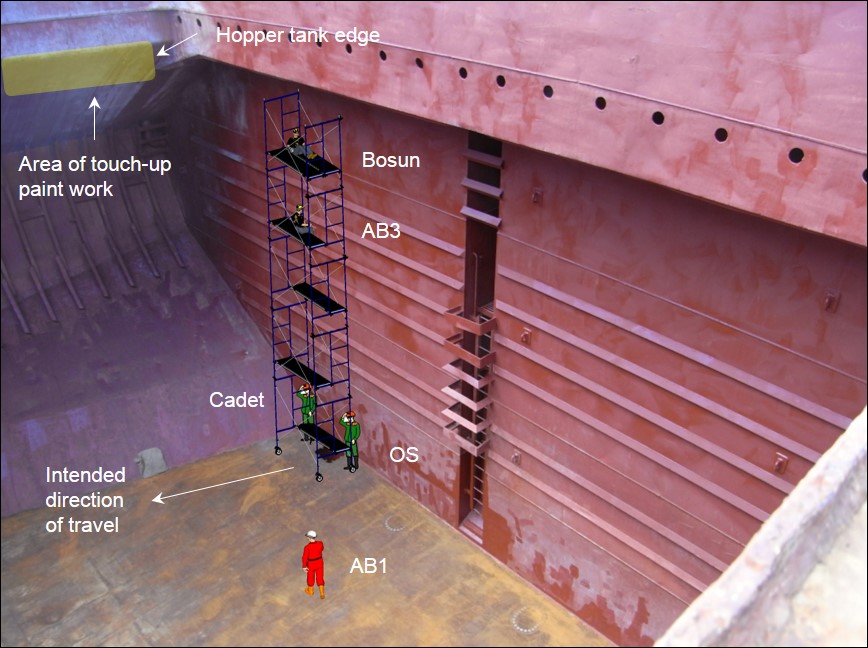
At the completion of the fifth move, the crewmembers were in position to finish the touch up of the aft bulkhead. The bosun was on tier five of the scaffold tower, about 8 m above the deck and AB3 was one tier below, facing aft, about 6 m above the deck.
After they had completed the work on the aft bulkhead, the bosun then decided to touch up the hopper tank edge (Figure 3). He instructed the OS and cadet to move the scaffold tower forward adjacent to the hopper tank edge, so they could reach the topside tank surface above.
Figure 3: Hold number four showing position of scaffold tower, crewmembers at completion of work and direction of next movement
Source: ATSB
The AB3 was aware the tower would be moved, and busied himself with clearing the equipment around him and lowering it to the tank top. Toward the middle of the hold, on the tank top, AB1 readied the equipment for the move. The cadet and OS released the tower securing lines and climbed down into the hold to move the scaffold tower.
At about 1410, the cadet and OS were in position either side of the base of the scaffold tower. They grasped the scaffold tower legs, released the wheel brakes and started to push the structure forward. The scaffold tower moved about 0.5 m when, without warning, it toppled forward to the deck, taking with it the bosun and AB3.
On hitting the tank top, the scaffold tower came apart and the bosun and AB3 were entangled in the components. AB1, the OS, and the cadet, hurried to assist the injured men.
The master was in his cabin at the time and heard loud noises coming from hold number four. He was unsure of the sound and went outside to investigate. On deck, he saw the scaffold structure and crewmembers on the tank top and he realised that an accident had occurred. He radioed the second officer on the bridge and directed that a public address announcement be made for all available crewmembers to go to the hold. He then went down into the hold to determine the details of the incident and the extent of any injuries.
The bosun and AB3 lay where they had landed on the tank top deck and were given assistance and first aid. The master then went to the bridge and commenced notifying his company’s Designated Person Ashore and the shipping agent.
At 1448, the agent and then, at 1449, the master, contacted Gladstone vessel traffic service (VTS) and notified them of the accident and requested assistance. The duty VTS officer then notified the Queensland Ambulance Service, the Gladstone Regional Harbour Master, and the Australian Joint Rescue Co-ordination Centre of the incident and the master’s request for assistance.
At 1504, emergency services were notified of the incident and tasked a rescue helicopter to retrieve the injured crewmembers. At the time of the tasking, the rescue helicopter was deployed on another mission, but was re-tasked to this job. The helicopter returned to base in Rockhampton where it was refuelled and reconfigured for winch and stretcher retrieval. The duty paramedic was briefed and, at 1558 the helicopter departed the base.
On board Shanghai Spirit, the injured men were moved to the main deck in preparation for their helicopter evacuation. At about 1700, the bosun, who had received more serious injuries, was winched to the helicopter and taken to Rockhampton Hospital. After refuelling, the helicopter returned to the ship at about 1830, retrieved AB3, and flew him to the hospital.
The bosun received multiple injuries to his pelvis, chest and arm. He remained in the hospital for 19 days before being repatriated. The AB3 sustained a fractured sternum and back injury. He remained in the hospital for 8 days before being repatriated.
At the time of the incident, Shanghai Spirit was registered in Hong Kong, classed with Nippon Kaiji Kyokai (NKK), and managed by Asia Maritime Pacific (AMP), Shanghai. It was on a regular service between ports in China, Japan and Australia, and frequently called at Port Alma.
The ship had a Chinese crew of 21. The master had 17 years of seagoing experience and held a Chinese master’s certificate of competency. He had sailed as master for 5 years and had been with AMP for the last 5 years. This was his second time on Shanghai Spirit, which he had joined about 2 months before the incident.
The chief mate had 19 years of seagoing experience and held a Chinese master’s certificate of competency. He had sailed on bulk carriers prior to joining AMP. This was his first time on Shanghai Spirit, which he had joined about 8 months before the incident.
The bosun and able seaman (AB) each had 12 years of seagoing experience on bulk carriers and general cargo ships. This was their first time with AMP and on Shanghai Spirit, which they had joined about 8 months before the accident.
AB1 had 11 years of seagoing experience on bulk carriers and general cargo ships. This was his first time with AMP and on Shanghai Spirit, which he had joined about 8 months before the incident.
The ordinary seaman (OS) had 18 months of seagoing experience. This was his second time with AMP and on Shanghai Spirit, and he had joined about 2 months before the incident.
The deck cadet had 8 months of seagoing experience and this was his first assignment on a ship.
Shipboard procedures
Safety management system
In compliance with requirements of International Safety Management (ISM) Code,[4] AMP had developed and implemented a Safety Management System (SMS) on board its ships. The stated intent of this system, amongst others, was ‘to ensure safety at sea, prevention of human injury or loss of life, and avoidance of damage to the environment, in particular to the marine environment and property…’.
The shipboard management and operation procedures provided general guidance for safe work on board. To ensure effective implementation of the SMS, all personnel, ashore and on board the ship, were directed to strictly obey the rules and regulations defined in the SMS documentation.
However, on 29 January the requirements of the SMS were not met. Crewmembers completing the task did not follow, nor complete required procedures, forms, or other documents.
During interview, crewmembers stated that a risk assessment and working aloft checklist had been completed for this work. Copies of these documents were provided to ATSB investigators on request. However, evidence collected from other sources suggested that the documentation may have been completed after the accident.
For example:
a Port State Control inspection conducted on 31 January 2017 could find no risk assessment or ‘working aloft’ checklist for this task
the ship’s crew could not supply copies of previous risk assessments and checklists for use of the scaffolding
the ship’s risk assessment file contained no risk assessments for scaffold use during the previous 18 months, despite the equipment having been used at least three times in the 6 months before this incident.
In addition to this, the master’s incident report to AMP identified that the risk assessment and working aloft procedures were not followed. That assessment was supported by AMP shore management. Additionally, the company issued a fleet circular in which failures to implement company procedures for risk assessment, for identification and planning of shipboard operations and for working aloft were identified as contributory factors in the accident.
Working aloft
Shanghai Spirit’s SMS contained procedures for key operations such as working aloft. The SMS classified working aloft as a special operation (when a dangerous situation exists) and required that ‘all mandatory international and national regulations’ be complied with. Notably, that the crewmembers be qualified for the task and that a risk assessment and maintenance plan be undertaken for that task using a defined process.
According to the ship’s SMS, such tasks as working aloft needed an ‘on the spot’ work assessment to determine the active risk and any preventative measures necessary to reduce that risk. Further, the work should be planned, crewmembers briefed, the checklist completed, and the operation be continuously supervised by an officer in charge of the work. Company requirements for working aloft required that special attention be paid to supervision and inspection of the work. The working aloft special instruction required the chief mate to be in charge and inspect the site for safe working. Further, the duty officer was required to be in attendance at the work site and supervise while the work was being completed.
Task sequencing
The task of painting and touching up hold surfaces was conducted during the morning and afternoon of 29 January. When interviewed, the master, chief mate and involved crewmembers confirmed the agreed task sequence was as follows:
scaffold tower assembled in position at the port aft corner of the hold
ladder frame pinned together, platforms in place on each tier, with wheel brakes engaged
OS and cadet go up onto the deck, run the scaffold guy ropes over the hatch coaming and secure them to strong points on deck
bosun and AB3 ascend the scaffold tower
safety harness lines run up to deck and secured by OS and cadet
work commenced.
As each area of work was completed, the scaffold tower required repositioning to access the next area.
The repositioning process to be followed was:
equipment secured on, or lowered from, the scaffold tower
OS and cadet release the safety harness securing lines
bosun and AB3 descend from the scaffold tower
OS and cadet release the scaffold tower securing lines
OS and cadet return to the hold bottom to assist with the movement of the scaffold tower as required
wheel brakes released and the structure repositioned
once repositioned, the process was reversed before work recommenced.
Code of safe working practice
According to the UK Code of Safe Working Practices for Merchant Seafarers, 2015 (COSWP),[5] the equipment should be of approved design and be rigged by competent persons in a recognised and/or recommended configuration to provide a safe working platform. The use of scaffolding is classed as ‘working at heights’ and therefore should be subject to planning and precautionary measures such as risk assessment and working aloft permits and precautions.
The ship carried a copy of COSWP that provided guidance for working at heights, with scaffolding, and provided reference to further information in the UK marine guidance notice (MGN 410M+F),[6] including but not limited to:
Personnel working aloft should wear a safety harness with a lifeline or other arresting device at all times.
If it is a mobile structure, it should be securely fixed to ensure that it cannot inadvertently move while in use.
The scaffolding shall be assembled and positioned to ensure its stability.
Wheeled scaffolding shall be prevented by appropriate devices from moving accidentally during work at height.
No seafarer is to be carried on any mobile work equipment unless it is designed for that purpose.
Subsequent to the incident, the ship’s managers provided an operating manual which detailed the steps for constructing a similar scaffold tower. Of note, the document detailed the correct assembly of the (similar) scaffold, personal safety information (safety belt, non-slip shoes, and safety helmet), and the requirement that all personnel are to disembark the scaffold during relocation.
Scaffolding
General information
The term ‘scaffold’ means any temporary structure, fixed, suspended or mobile, and its supporting components, which is used for supporting workers and materials, and which is not a lifting appliance. Mobile scaffolding is regularly used by ships’ crew to conduct maintenance of normally inaccessible (high) areas on board. Such equipment is particularly useful for hold maintenance such as chipping and painting of upper surfaces.
On board equipment
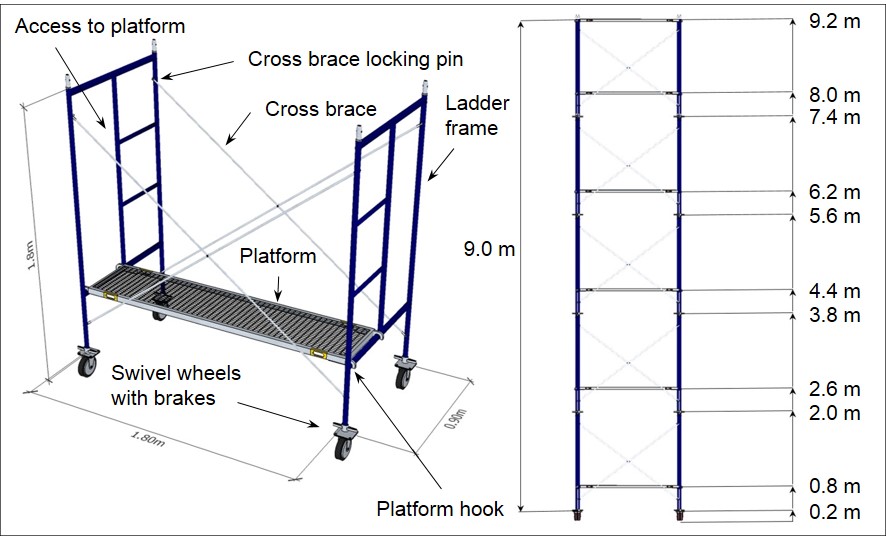
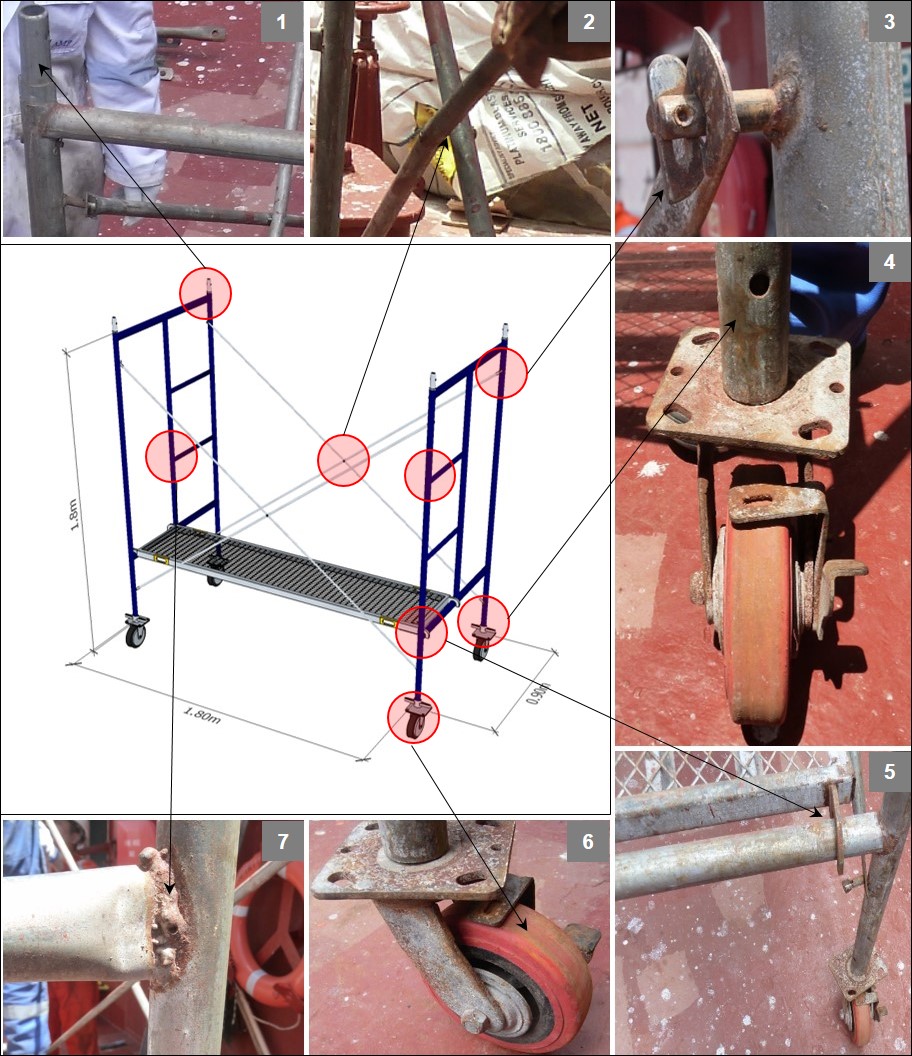
The mobile scaffolding equipment in use on board Shanghai Spirit was made of steel and was similar to other common types of mobile scaffold towers designed for use on stable, level surfaces. It was constructed of modular tiers placed one atop the next via inserts in each vertical leg. Each tier was 0.9 m wide, 1.8 m long and 1.8 m high. With five tiers fitted, the scaffolding had a height of 9.2 m. A single, half-width (400 mm wide) work platform was positioned on the lower cross bar of each tier with two in place on the uppermost (fifth tier) level (Figure 4).
Figure 4: Scaffold construction components and dimensions
Source: ATSB
At the base of the scaffold, rubber-tracked swivel wheels were fitted at each corner and allowed the structure to be moved (rolled) easily from position to position. These wheels could be locked to prevent unintended movement.
On board inspection of scaffolding equipment
Inspection of Shanghai Spirit’s scaffolding equipment (Figure 5) identified that it had no manufacturer’s identification plate, and all components showed signs of regular use, wear, damage, and some repairs.
The following defects were found during an on board inspection:
ladder frame stub piece connections without securing pins
loose and bent cross bracing
cross brace locking pins loose allowing travel up to with 40 mm
swivel wheels stub piece connections without securing pins
corroded platform hooks
inoperative swivel wheel brakes on three of the four wheels
deficient frame ladder welds.
Figure 5: Condition of the scaffold tower
Source: ATSB
Scaffolding documentation
The scaffolding equipment used on board should be supported by suitable documentation such as operating and maintenance manuals, guidelines and training materials. The equipment should, only be used by competent, trained personnel and should be regularly inspected and maintained. Documents specific to the scaffold tower onboard were not identified during the investigation. Some additional documents, including test certificates, were subsequently provided by the company. However, these documents were found to be for mobile scaffolding equipment of a different design and not for that in use on the ship at the time of the accident. The scaffolding certificate showed the equipment was last tested in 2013, and had been on board for about 4 years.
Related occurrences
The ATSB has investigated similar occurrences on board ships at anchor in 2003 and 2009.
Pacific Wisdom was a 1992-built geared bulk carrier with five cargo holds. The ship’s holds were serviced by four cranes. On 5 September 2003, the ship arrived at Albany and anchored in the outer harbour. As it was due to load wheat, the ship’s crew started preparing the holds for cargo loading. This involved washing each hold and scraping and touching up the interior paintwork ready for the grain cargo.
The ship’s crew used a mobile scaffold tower to access the areas around top of the hold and under the main deck. The work progressed over the next few days, working from forward to aft in the holds.
On 7 September 2003, after moving the scaffold tower to the aft end of a hold, two crew members climbed the scaffold tower to resume their work. However, as soon as they had climbed onto the platform at the top of the scaffold tower, the entire tower fell towards the aft bulkhead. The two men fell about 12 m to the tank top resulting in the death of one crew member and serious injuries to the other.
The following findings from that accident are particularly relevant to this occurrence:
The base of the scaffolding was too narrow for the assembled height, making the scaffolding inherently unstable.
Guy ropes were not secured, and the castors were not locked prior to the men going back up the tower.
The two men had not secured their safety harnesses to the ship’s structure.
It is probable that some combination of ship movement in the seaway and the distribution of weights at the working platform level were factors in the fall of the scaffolding.
In an attempt to hasten the work in hand, both company procedures and normal seaman-like practices were not followed.
Serious injury on board United Treasure off Port Kembla, New South Wales on 7 July 2009 (266-MO-2009-005)
United Treasure was a 2006-built gearless bulk carrier with 7 cargo holds. On 23 June 2009, the ship anchored off Port Kembla, Australia, waiting for a berth to load coal. Expecting many days at anchor waiting for a berth, the master thought it would be a good opportunity to paint the empty cargo holds.
On 24 June, work started in number four hold. Scaffolding was used to access higher areas in number four hold. The scaffold tower was moved in the hold and its height adjusted as required.
By 4 July, work had been completed in holds number four, three and two and had progressed to number one hold. However, the weather conditions deteriorated and work was suspended for several days due to the moderate to heavy rolling and pitching.
On 7 July, the weather had abated slightly and the ship’s master instructed the crewmembers to progress number one hold. After the crew members had assembled the scaffold tower, they started to heave up the painting equipment. However, the ship rolled and the scaffold tower swayed. Shortly after, the scaffold tower toppled to port and crewmembers fell with it to the tank top, 8 m below. Both men sustained compound fractures and were evacuated from the ship by helicopter and taken to hospital.
The following findings from that accident are also relevant to this accident:
The mobile scaffold tower was not secured to the ship’s structure and it toppled over when United Treasure rolled and the seamen began lifting equipment up from the tank top.
The seamen were secured to the tower instead of a strong point on the ship’s structure using a safety harness with a fall arrestor.
Locking the tower’s wheels and using safety belts indicates that some risks were identified but not effectively securing the tower suggests an assumption that it would not topple over. The inadequate and/or ineffective precautions taken indicate that an appropriate risk assessment was not carried out.
United Treasure’s permit to work aloft system had not been effectively implemented on board the ship.
The tower was not assembled as designed. The outriggers and intermediate planks, both key components, were missing and the work platform guard rails were not used. The manufacturer’s instructions were also missing, and no attempt was made to obtain them, a parts list or the missing parts.
Throughout 29 January 2017, deck crewmembers on Shanghai Spirit were conducting painting and routine touch-up work in the cargo holds, utilising a mobile scaffold tower. The contrast between how this activity was conducted in the morning compared to the afternoon highlights the key element of this accident. That is, contrary to company procedures, accepted practice and industry guidance, the two crewmembers remained unsecured on the scaffolding while it was repositioned within the hold.
It was reported that the occurrence day was hot (32° C) and the worksite was uncomfortable, in an open hold with poor natural ventilation. As a result, the decision to remain on the scaffold tower was probably motivated by a desire to expedite completion of a task being conducted in difficult working conditions.
That decision to remain on the scaffolding however, led to it being top-heavy and unstable when the supporting lines were not secured. Scaffold repositioning for the majority of the previous work was port to starboard in the direction of the scaffold’s longest base dimension. That direction of movement provided sufficient stability to protect against overbalance and toppling, compared to when it was moved in the fore-aft direction along the narrowest base dimension, in order to reach the hopper tank edge.
Consequently, when the unsecured scaffolding and occupants were moved towards the hopper tank edge it toppled and fell.
Use of safety equipment
During the morning in hold number one, the crewmembers operating from the scaffold tower donned safety harnesses however safety lines were not attached before the crewmembers climbed or descended the structure. Instead, the lines were passed down and connected to the harnesses once the crewmembers were at their working positions. Therefore, if the crewmembers had fallen from the scaffold during ascent or descent, their fall could not have been arrested.
During the afternoon task neither crewmember utilised the available safety harnesses or lines so they were not protected in the event of a fall while climbing the scaffold or when they were at their working positions. If the harnesses and the associated safety lines had been in use when the scaffolding fell the two crewmembers may have still have been seriously injured as their safety lines may have become fouled in the collapsing scaffold.
Task supervision
During the afternoon’s work there was no appointed supervising ship’s officers so, by default, the most senior crewmember was deemed to be responsible for the conduct of the task. However, that individual was one of the two crewmembers working from the scaffold tower who did not come down during its repositioning, despite being required to do so. As these same crewmembers had also worked from the tower in the morning and climbed down during each repositioning, the ATSB concluded that they were both familiar with the requirement to climb down from the scaffolding before it was moved. In that context, the decision to remain on the scaffolding during the afternoon repositioning was probably influenced by the lack of formal supervision, as well as the desire to expedite the task detailed above.
Working from a scaffold tower is ‘work at height’, and research conducted by the UK Health and Safety Executive shows that falls from height usually occur as a result of poor management control rather than because of equipment failure. The success of shipboard tasks such as hold maintenance relies heavily on the actions, behaviours and relationships of the people involved in the task. This accident highlights the importance of adhering to procedures that assure safety as well as the value of effective supervision.
Scaffolding condition
Examination of the scaffold tower following the accident identified a number of defects relating to damaged, loose, corroded and unserviceable components.
While these defects would undoubtedly have reduced the tower’s rigidity and stability, it was successfully repositioned during the morning activities, and the majority of the afternoon task with the crewmembers on it, without toppling. That indicated that, despite these flaws, it was sufficiently stable during those moves. Therefore, while the identified defects may have contributed to the accident when it was moved towards the hopper tank edge, the lack of stability associated with movement of the tower in the fore-aft direction along the narrowest base dimension with crewmembers on it, may alone have resulted in it falling.
While it could not be determined whether the condition of the scaffold tower contributed to this accident, for equipment to be suitable for use on board a ship, it must not only be in good condition and fit for purpose, but should comply with relevant standards and be suitable for the work which is to be carried out.[7]
Shipboard procedures and documentation
The on board guidance for scaffold use consisted of an ‘operation manual’ page. While this document proved to be for equipment of different design to that being used on Shanghai Spirit, it did contain the following relevant safety precautions:
workers on the scaffolding should wear protective equipment including a safety helmet and safety harness (belt)
the scaffolding should not be moved with persons on it.
These precautions, if adhered to, would probably have prevented the accident from occurring. In that regard, the fact that the operations manual page referred to a different equipment design did not in itself contribute to the accident.
Shanghai Spirit’s scaffolding equipment was not supported by suitable documentation, and therefore did not ensure guidance for the correct methods and level of maintenance, tracking of maintenance and repair history, or provide training and familiarisation guidance. Had this supporting information been available, it would most likely have provided an opportunity for guidance relating to rectification of the identifed damage and wear, and sound methods for its safe operational use.
The ship carried the UK Code of Safe Working Practices for Merchant Seafarers, 2015 (COSWP). This document contains best practice guidance for improving health and safety on board ship. Chapter 17 referred to Work at Height including a specific section and annex on scaffolding. This chapter outlined guidance for such things as scaffold plans, ensuring tower stability, preventing accidental movement, fall prevention and appropriate and specific scaffold/rigging training.
Furthermore, the COSWP section on carrying seafarers on mobile work equipment stated that ‘No seafarer is to be carried on any mobile work equipment unless it is designed for that purpose’. If the guidance contained in the scaffold operation manual page, and/or COSWP had been heeded, the accident and resulting crewmember injuries would not have occurred.
The appropriate methods of attaching safety lines should have been considered, and the lines attached to the crewmembers before they climbed the tower and this practice followed in the afternoon.
From the evidence available, the following findings are made with respect to the fall from height and serious injury of two crewmembers aboard Shanghai Spirit during a maintenance task, while at anchor 15 nautical miles north‑east of Port Alma, Queensland on 29 January 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
Contrary to established procedures, two crewmembers remained on the unsecured scaffold tower in preparation for repositioning, rendering it top‑heavy and unstable. Consequently, when moved it toppled and fell.
The afternoon work in hold number four was not supervised by an officer as required by company procedure and in contrast to the morning activity. The absence of formal supervision, in combination with a desire to expedite the task in difficult working conditions, probably led to the crewmembers remaining unsecured on the scaffolding as it was repositioned.
Other factors that increased risk
The assembly and condition of the scaffold tower had several defects, which exacerbated the unstable state of the structure.
Guidelines for the provision, care and use of the scaffold tower, was not supported by suitable on-board documentation. The only documentation was for mobile scaffolding equipment of a different design, and not for that in use on the ship. [Safety issue]
Neither crewmember on the scaffold tower utilised the required safety harness and associated safety lines which would have prevented them falling when climbing or working on the tower.
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to initiate safety action proactively, rather than to issue formal safety recommendations or safety advisory notices.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
The initial public version of these safety issues and actions are repeated separately on the ATSB website to facilitate monitoring by interested parties. Where relevant the safety issues and actions will be updated on the ATSB website as information comes to hand.
Guidelines for the provision, care and use of shipboard equipment were not supported by suitable documentation. The only documentation was for mobile scaffolding equipment of different design and not for that in use on the ship.
Additional safety action
Following this accident, the ATSB was advised the following addition safety action has been taken:
The use of scaffolding is now specifically classed as ‘working at heights’ and is therefore subject to all planning and precautionary measures such as risk assessment, working aloft permits and precautions.
Personnel Protective Equipment training and awareness has been reviewed and enhanced. Additionally, new crewmembers will be subject to pre-joining training that now includes the use of scaffolding.
General details
Ship details
Name:
Shanghai Spirit
IMO number:
9326328
Call sign:
VRD04
Flag:
Hong Kong, the People’s Republic of China
Classification society:
ClassNK
Ship type:
Geared bulk carrier
Builder:
Yamanishi Co, Ishinomaki, Japan
Year built:
2005
Owner(s):
Shanghai Spirit Shipping Ltd
Manager:
Asia Maritime Pacific (Shanghai)
Gross tonnage:
11,751
Deadweight (summer):
18,829 t
Summer draught:
8.44 m
Length overall:
139.92 m
Moulded breadth:
25.00 m
Moulded depth:
11.50 m
Main engine(s):
Makita – Mitsui MAN B&W 7S35MC (Mk 7)
Total power:
5,180 kW, 173 rpm
Speed:
13.0 knots
Sources and submissions
Sources of information
The sources of information during the investigation included:
the master and involved crewmembers of Shanghai Spirit, including the injured persons
Asia Maritime Pacific (Shanghai)
the Australian Maritime Safety Authority
the Capricorn Helicopter Rescue Service
Maritime Safety Queensland
the Marine Department, Hong Kong, the People’s Republic of China.
Rolfe ST, Barsom JM 1977, Fracture and fatigue control in structures, applications of fracture mechanics, Prentice-Hall New Jersey, pp. 414-440.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Asia Maritime Pacific (Shanghai), the Australian Maritime Safety Authority, Maritime Safety Queensland, the Marine Department of Hong Kong and the master, chief mate, bosun and AB3 on board Shanghai Spirit.
Submissions were received from Asia Maritime Pacific (Shanghai), the Australian Maritime Safety Authority and Maritime Safety Queensland. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 13 December 2016, a Virgin Australia Boeing 737-800 aircraft, registered VH-VUF, was being prepared to operate flight VA 1393 from Adelaide, South Australia to Brisbane, Queensland.
At 0927 Central Standard Time (CST), the graphical load instruction report (GLIR) was sent to the ramp staff allocated to load the aircraft. Virgin Australia used an electronic load control system (LCS), which was accessed by the leading hand on a mobile tablet device to organise the loading of the aircraft.
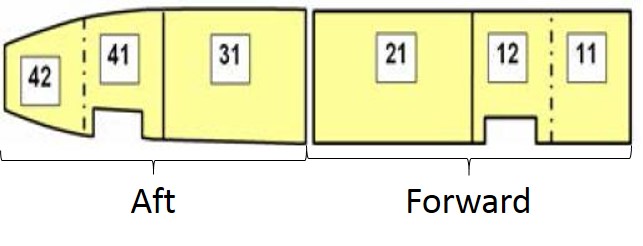
The GLIR indicated the Brisbane bound bags and all cargo (seafood and four dogs) were to be loaded in the forward compartment (section 21), and the bags which would be transferred to connecting flights and the priority Brisbane bags were to be loaded in the aft compartment (section 31) (Figure 1).
Figure 1: Compartments of a Boeing 737-800
Source: Operator (modified by the ATSB)
While loading the aircraft, a member of the loading staff advised the leading hand that the Brisbane bags would not fit into the compartment with the cargo unless they were placed on top of the dog crates. If the bags were placed on the crates, the loading staff thought the dogs may not have enough oxygen to breathe. To resolve this issue, the leading hand used the LCS to move 55 bags into section 31, and saved the changes in the system. When the changes were made, the ‘Move Mode’ and the ‘Ramp Clear Mode’ buttons on the tablet’s screen greyed out and the load control status changed to ‘LL’.[1] The loading staff proceeded to load these bags in section 31. When the leading hand refreshed the device after the bags had been moved, the status returned to normal and the leading hand presumed the changes had been accepted.
At about 0938, the load controller in Brisbane noticed an approval request in the LCS (for the load to be redistributed). This request was for 55 bags (equal to 870 kg) to be moved from section 21 to section 31. The LCS will allow the leading hand/load supervisor to move up to 500 kg of freight provided the centre of gravity moment does not change by more than 5 index units[2] without the approval of the load controller only if the resultant centre of gravity remains within operational limits. However, as this amount exceeded the limits, the change needed to be approved by the load controller. Two indications were generated by the LCS for the leading hand indicating the system was locked and the take-off index was exceeded (greying out of the ‘Ramp Clear Mode’ and ‘Move Mode’, and the load control status change to LL).
A high priority message was also shown on the load controller’s screen stating the take-off index had exceeded the aft limit by 4.8 index units. This meant the aircraft was no longer within the required centre of gravity limits. In response, the LCS was locked for 7 minutes while the load controller calculated the required changes to the load and approved the changes in the LCS.
The load controller calculated that moving 40 bags from section 31 of the aircraft back to section 21, or moving a number of passengers forward, would be enough to return the aircraft to balance.
Because the leading hand was using the mobile application, the load controller thought they had a direct line of communication with the leading hand so they used the in-built messaging system to send a message. The message the load controller wrote was the request to move the bags was denied and the solution was to move passengers or to put 40 bags in section 21. The load controller received no response from the leading hand and amended the LCS. The flight information was then unlocked so the ground crew could continue to update the LCS. The leading hand did not receive these messages and they subsequently finalised the flight, without making any changes or checking the LCS, and the final documents were released by the LCS automatically. This indicated the changes had been accepted and the aircraft had been loaded correctly.
After the aircraft had departed, the leading hand was re-checking the paperwork and saw the bags had been moved in the LCS back to section 21 by load control. The leading hand then spoke to the airport movement co-ordinator (AMCO). The AMCO attempted to contact the aircraft by radio, but received no response.
The AMCO then contacted the load controller to explain what had happened. The load controller determined the aircraft was out of balance by 4.8 index units past the aft limit for take-off and the flight crew should be advised 40 bags (equal to 626 kg) were in section 31, not section 21.
To return the aircraft to balance, the load controller advised the AMCO that three passengers would have to move forward from zone D to zone B. When the flight crew rang for the departure call, the AMCO passed on this information, however, when asked to confirm they had received this information, there was no response. Flight dispatch then contacted the flight crew via satellite phone and confirmed the flight crew had received this information. The flight crew contacted the cabin supervisor with the request to move three passengers forward. There were no control issues during flight.
Loading procedures
Virgin’s airport airside operations manual included the following steps in regard to loading aircraft:
Loading aircraft
The load supervisor/leading hand/delegate confirms the final load is loaded in accordance with the final loadsheet and this is reflected in the loading report (LDR).
Live animals loading/unloading
All ramp staff are responsible for monitoring and protecting the welfare of live animals.
Baggage and/or cargo must not be loaded on top of cages and ventilation holes on the cages must not be covered.
Load control system
Subscribe to flight
Before a flight is selected to work on, the user must first subscribe and add themselves to it. This is needed to ensure any messages regarding the flight are received and it also adds the users contact details.
Identifying compartment overloads
Compartments will only display in red on the LCS, if the leading hand/AMCO/delegate makes a change to the deadload[3] that exceeds the compartment weight or volume.
Deadload change ramp tolerance
Changes can be made to a flight’s deadload on the LCS without having to verbally communicate with load control. The change to the deadload weight for a Boeing 737, in the operator’s system, is limited to 500kg when the change to the centre of gravity moment is no more than 5 index units and the resultant centre of gravity remains within operational limits.
Changes that are made outside these tolerances will need to be approved by load control. The notification is sent automatically to load control for their approval.
If load control denies the change request, e.g. out of balance, then a phone call will be made to the port to advise. If the change is approved, the leading hand/AMCO/delegate will see this approval by viewing the load control flight status.
As a result, if changes are required above the pre-determined tolerances, the leading hand/AMCO/delegate should contact the load controller for the flight by either phone or by using the message screen.
Out of balance
Virgin’s load control standard operating procedures included the following steps in regard to solving out of balance situations:
Contact the leading hand/delegate with the requirements advising what deadload and in which compartment it needs to be moved to.
The leading hand/delegate is responsible for ensuring the deadload is redistributed as advised and updated in the mobile application to reflect the changes.
Operator report
The operator conducted an internal investigation with the following findings:
If the aircraft is out of trim, overweight or the move exceeds the pre-set tolerance (500kg and/or five index units) allowable for a ramp agent the change, as long as it is acceptable, may be approved by the load controller. Any change requiring load control acceptance, is indicated by the ‘Move Mode’ and ‘Ramp Clear Mode’ buttons becoming ‘greyed out’ and not being accessible. In addition to this, the load control status at the top of the screen changes to ‘LL’ (Load Control Closed-Approve Distribution required). The leading hand recalled being unsure of what the load control status meant.
The load controller used the flight management loading system to move the 40 bags to compartment 21. The screen on the mobile application was refreshed a short time later with the ‘Move Mode’ and ‘Ramp Clear Mode’ button becoming active, indicated by the buttons having a green border and text. The leading hand believed the ‘Move Mode’ and ‘Ramp Clear Mode’ buttons had become active after the refresh of the screen as a result of their original change.
The visual aids incorporated into the flight management mobile application alone are not effective in preventing a configuration misalignment.
Load controller comments
The load controller provided the following comments:
They thought using the messaging system was the best way to communicate with the leading hand given they had just made the change in the system and thought they had a direct line of communication via the messaging system.
The GLIR is automatically generated by the system.
Leading hand comments
The leading hand provided the following comments:
Making changes to the load plan is considered a last resort and only if necessary. This is emphasised given this incident.
Once the changes were made in the LCS, they assumed the changes were accepted and did not double check the figures accurately. Cross checking the LDR and the actual load is part of the procedure.
There have been instances in the past where the load plan has not been practical, but it can be difficult to predict because they do not always know about the size of the bags, for example.
AMCO comments
The AMCO provided the following comments:
To receive messages within the system, you must add and subscribe to the flight you are currently loading. Because the leading hand was not subscribed to the flight, they did not receive the messages.
It is possible to enter into flights within the system without subscribing as it is not a compulsory screen. It is also possible to enter flights without realising you have not subscribed.
The load controller advised based on the fuel usage, the aircraft would be in trim for landing.
Previous occurrences:
A search of the ATSB database of previous loading related occurrences involving incorrect load or weight on the aircraft were detected, particularly when procedures were not followed during the process and discrepancies were not identified in the load sheet:
Loading related event, Bali, Indonesia, 26 May 2014 (ATSB investigation AO-2014-110).[4] A Boeing 737 aircraft was being loaded at Bali Airport for a flight to Melbourne, Victoria. Due to the time restrictions, the ground staff were unable to load all of the bags for the flight before aircraft had to be prepared for departure. The load controller assessed a total of 93 bags had been loaded and the flight documents produced were using that figure. About 30 minutes after the aircraft departed Bali, the ground handler advised network operations and load control the final baggage numbers were incorrect. The total number of bags loaded onto the aircraft was 189 instead of 93, which an estimated additional weight of about 1,600 kg. Prior to loading, the ground crew were under time pressure due to the flight already being delayed, breakdown of a baggage belt, scheduled closure of the runway, and impending airport curfew.
Loading event, Sydney Airport, New South Wales, 8 September 2016 (ATSB investigation AO-2016-119).[5] An Airbus A320 was being loaded at Sydney for a flight to Brisbane, Queensland. The leading hand received the deadload weight statement (DWS) and checked the containers. The third container number (1483) did not match the number listed on the DWS (4183), nor the container card (4183). The leading hand assumed the freight handler had inadvertently transposed the numbers incorrectly and amended the card and DWS with 1483 and continued loading. When the aircraft was unloaded in Brisbane, it was found that the incorrect container (1483) was delivered and was nearly 650kg heavier than container 4183. The loading procedure if the DWS is incorrect is the container must not be loaded onto the aircraft. The leading hand noted the short turnaround time and the flight was the last one of the day led to procedures being bypassed.
Safety analysis
The first step for users in the LCS is to subscribe and add themselves to the flight. This is undertaken to ensure the messages are received by people within the network, such as AMCOs, load controllers, freighters, and leading hands. This is not a compulsory page in the LCS and can be skipped when opening a particular flight. The leading hand had not subscribed to the system, meaning they did not receive the messages from the load controller about the aircraft being out of trim due to the movement of baggage from section 21 back to section 31.
When the baggage from section 21 was moved to section 31 by the leading hand in the LCS, the system locked. This was indicated on the LCS display by the buttons being greyed out and the load control status at the top of the screen changing to ‘LL’. This did not provide clear indications that the load distribution change needed acceptance by the load controller before proceeding with loading the aircraft. The leading hand was not sure what the load control status meant. Furthermore, as the system returned to open when they reset the system they did not realise that changes had been made in the LCS.
The load controller received an error message in the system because the number of bags moved by the leading hand meant that the aircraft was out of balance. The load controller attempted to contact the leading hand via the messaging system but was unaware the leading hand was not subscribed to the system so the messages were not received.
The operator had two procedures for load control to notify the leading hand that changes have been made in the LCS. The 'deadload change ramp tolerance’ in the standard operating procedures for the flight management mobile application required that load control make a phone call to advise the leading hand or the AMCO that they had denied a change request through the LCS. The second procedure, which is in the controlling document used by load control, for ‘out of balance operations’ required that load control communicated the requirements to the leading hand (which was normally done through the messaging system within the LCS). In this incident, the load controller used the messaging system which was not effective as the leading hand was not subscribed to the system.
Once the loading is completed, it is the leading hand’s responsibility to confirm that the LDR reflects how the aircraft has been loaded. Although the leading hand did check, they did not detect the error until after the aircraft had departed.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The leading hand was not subscribed to the load control system, meaning they did not receive the messages from load control about the aircraft being out of trim and subsequent change to the load distribution.
Although the load control system locked after the leading hand made changes to the load distribution, it did not provide sufficient feedback to the leading hand to indicate that the changes needed to be accepted by the load controller before proceeding.
Although the controlling document for load controller noted that contacting the leading hand was required due to an out of balance situation, another document regarding the loading system specified a phone call was to be made.
The leading hand did not accurately cross check that the aircraft was loaded in accordance with the LDR.
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Operator
As a result of this occurrence, the aircraft operator has advised the ATSB they are taking the following safety actions:
Safety bulletin: subscribing to flights
The operator has issued a safety bulletin for leading hands to subscribe to the flight management system.
Due to recent occurrences throughout the network, it has highlighted the requirement to ensure leading hands subscribe to flights which they are assigned to, in the Flight Manager Program.
Subscribing to a flight attaches your contact details to the flight.
This will allow messages to be sent between you and load control. Once subscribed to a flight you will receive a conformation pop up message. You can subscribe to more than one flight at a time.
Safety bulletin: changes to deadload
The operator has also issued a safety bulletin about making changes to deadload:
It is very important that changes made to the planned deadload remain at a minimum, and they must only be made if deemed absolutely necessary – i.e. if there are concerns with the safety of the flight or there is restricted volume in the aircraft hold.
If changes are required above the pre-determined Deadload Change Ramp Tolerances, the Leading Hand/AMCO/Delegate should contact the Load Controller for the flight by using the message screen in the Ramp Application, or if this is not possible, by phone. It is important to read and acknowledge all messages received from the Load Controller.
System functionality
New system functionality is being introduced where a leading hand allocates him/herself to a flight and therefore no one else has access.
Safety message
This incident highlights the importance following procedures and communication have during the loading process. Communication when there is an error is particularly important to ensure all team members share the same understanding of the error and the correction. The ATSB report: Aircraft loading occurrences - July 2003 to June 2010 identified loadsheet errors as contributing to these occurrences.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 20 January 2017, a British Aerospace AVRO 146-RJ85, registered VH-NJW, conducted a charter flight from Perth to Darlot, Western Australia (WA). There were four crew and 58 passengers on board the aircraft. The captain was the pilot flying (PF), seated in the left seat, and the first officer was the pilot monitoring (PM), seated in the right seat.[1]
The aircraft departed from Perth Airport at about 0630 Western Standard Time (WST) and tracked towards Darlot. Prior to the top of descent, the flight crew obtained the local weather from Leinster Airport, situated about 28 NM (52 km) from Darlot. The Leinster aerodrome weather information service (AWIS)[2] indicated a strong easterly wind, so the PF positioned the aircraft to join a 5 NM (9.3 km) straight-in approach to runway 14.
Darlot Airport had an unsealed runway with no electronic approach path guidance with a published RNAV-Z (GNSS) runway 14 approach. The procedure for the crew to monitor their descent profile was to crosscheck the distance and altitude information from the published approach chart, which provides a 3° descent on final approach. Three white cones, located on the left and right side of the runway strip and 300 m in from the runway threshold, provided the pilot with their visual aiming point markers for the landing. Therefore, on short final, the PF would change their flight path guidance cue from distance and altitude to the aiming point markers for the aircraft landing.
When the aircraft joined the final approach leg, the PF noticed dust in the vicinity of the runway and commented to the PM that there could be a vehicle on the runway. At about 2.5 NM (4.6 km) from the runway, the PF concluded the dust was not from a vehicle and that it was a line of dust from the strong easterly wind, which extended the length of the runway strip,[3] on the southern side of the runway. At about the same time, the PF visually identified the runway[4] markers.[5] On short final, the PF transitioned from the distance-altitude information to the aiming point markers located on the left side of the runway strip.
The aircraft landed without incident. However, as the aircraft slowed to taxi speed, the PF observed cones and runway lights on the right side of the aircraft, but only cones on the left side of the aircraft. The PF then noticed that the raised dust on the right side of the runway strip covered both the runway markers and runway strip (Figure 1). They had landed the aircraft on the graded area of the runway strip to the left of the runway. The PF manoeuvred the aircraft back onto the runway, taxied to the apron and shutdown without further incident. The aircraft was not damaged.
Figure 1: Darlot Airport runway 14
Source: Pilot, annotated by ATSB. Image depicts Darlot Airport runway 14 and left side of runway strip as viewed from the right seat of the aircraft with white frangible cones used as markers. Raised dust extends from the centre of the runway across the southern side of the runway strip.
Aerodrome markers
The Manual of Standards (MOS) Part 139 – Aerodromes, provided the standard for aerodrome markers. In accordance with MOS 139 paragraph 8.2.1.1, ‘markers must be lightweight and frangible; either cones or gables.’
Runway markers
Darlot Airport used identical white frangible cones as markers for both the runway and the runway strip. The runway was 30 m wide and 1,969 m long. The runway strip was 90 m wide. Therefore, the lateral spacing of the cones for the runway and the runway strip either side of the runway were equidistant.
Aiming point markers
In accordance with MOS 139 paragraph 8.3.7, on sealed runways, aiming point markers are conspicuous stripes painted on the runway surface. If a visual approach slope indicator system (VASIS) is used, then the VASIS is located within the runway strip and the beginning of the aiming point marking must coincide with the origin of the visual approach slope.
Where aiming point markers are not required, such as on unsealed runways, the airport operator can elect to ‘implement an aiming point marking by providing an appropriate marking.’ Darlot Airport used three frangible white cones, either side of the runway on the edge of the runway strip, as aiming point markers (Figure 1).
Objects on runway strips
MOS 139 paragraph 6.2.24 stated ‘A runway strip must be free of fixed objects, other than visual aids for the guidance of aircraft or vehicles. All fixed objects permitted on the runway strip must be of low mass and frangibly mounted.’
Location of aiming point markers
The aircraft operator provided services to three other airports with unsealed runways. Following this incident, the operator reviewed the other airports and found that at two airports the aiming point markers were located inside the runway strip (one used gable markers and the other cones), either side of the runway (Figure 2), and at the third airport the aiming point markers had been removed. Therefore, the aiming point markings were inconsistent between all four airports.
Figure 2: Gable aiming point markers within the runway strip (different airport used by the operator)
Source: Aircraft operator
In 2015, the Darlot Airport operator consulted with the Civil Aviation Safety Authority about the position of the aiming point markers. It was determined that they were not standard markings. Therefore, the airport operator could request a dispensation from MOS 139 to place them in the runway strip next to the runway, or alternatively, place the markers outside the runway strip without a dispensation. The airport operator passed this information on to the aircraft operator, and it was agreed to place them outside the runway strip, in lieu of requesting a dispensation.
Visual illusions
According to the Flight Safety Foundation, visual illusions occur ‘when conditions modify the pilot’s perception of the environment relative to his or her expectations, possibly resulting in spatial disorientation or landing errors.’ The key factors and conditions which result in visual illusions are the airport environment, runway environment and weather conditions.
Further information on visual illusions is available from the Flight Safety Foundation approach-and-landing accident reduction tool kit Briefing Note 5.3 - visual illusions.
Safety analysis
The PF advised that the final approach to land at Darlot, was a period of high workload because the aircraft was flown manually with cross-checks of distance and altitude used to manage the descent profile. On the incident flight, the PF’s attention was initially captured by raised dust, which indicated to the PF that there could be a vehicle on the runway. About halfway down the final approach, the PF discounted the presence of a vehicle, but then incorrectly identified the left runway strip markers as the left runway markers because the right runway and runway strip markers were obscured by the raised dust. This was confirmed in their mind by the presence of the aiming point markers on the left side of the runway strip. The PF was seated in the left seat and therefore used the aiming point markers on the left side as their visual guidance cue for the aircraft landing.
The siting of aiming point markers at airports with unsealed runways used by the aircraft operator was not standardised with respect to the type of markers used or the position of the markers relative to the runway. The pilot had experience, from operating into other unsealed runways, of aiming point markers positioned in the runway strip next to the runway. Therefore, the position of the aiming point markers on the left side of the runway strip markers was not recognised by the PF as an indicator that the aircraft was landing to the left of the runway.
ATSB comment
On approach to land, the PF must scan between the near end and far end of the runway for their visual judgement of flare height and alignment of the aircraft with the runway centreline. A greater amount of visual processing is dedicated to the central region of the retina (fovea) than to the peripheral regions of the retina. Consequently, central portions of a visual image are seen to a higher resolution than peripheral portions.
For a pilot focused on the runway centreline, the aiming point markers will move from central vision to peripheral vision at three times the distance for markers laterally displaced 45 m in lieu of 15 m from the runway centreline.
The ATSB notes that the aiming point markers are a visual guidance cue for the PF. Increasing the lateral displacement of the markers from the runway may divert the PF’s scan further from the runway centreline at a critical stage of flight.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The PF landed the aircraft in the runway strip to the left of the runway due to raised dust obscuring the markers on the right side of the runway and runway strip.
Aiming point markers were employed in a non-standard manner at the unsealed runways used by the operator, which may have contributed to the PF landing the aircraft left of the runway.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Operator
As a result of this occurrence, the aircraft operator has advised the ATSB that they have taken the following safety actions:
Internal investigation and review
The operator has conducted their own internal investigation of the incident, which included a review of the unsealed runways they operate the AVRO 146 into.
Discussion paper
The operator submitted a discussion paper to the Civil Aviation Safety Authority on the provision of aiming point markers for unsealed runways. The paper proposes the standardisation of aiming point markers in accordance with the system previously tested by the United States Federal Aviation Administration.
The results of the testing can be found in ‘Marking and Lighting of Unpaved Runways – Inservice Testing’: DOT/FAA/CT-84/11.
Safety message
Following the incident, the pilot reported that, in hindsight, the raised dust they observed on the runway strip should have led to a go-around manoeuvre, but their visual cues led them to believe they were aligned to land on the runway. The Flight Safety Foundation briefing note 5.3 provides strategies for pilots and operators to mitigate the risk of a visual illusion incident during approach and landing.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 26 January 2017, the pilot of a Grumman American Aviation Corp G-73 amphibian aircraft, registered VH‑CQA (CQA), was participating in an air display as part of the City of Perth Australia Day Skyworks event. On board were the pilot and a passenger. The pilot of CQA was flying ‘in company’ with a Cessna Caravan amphibian and was conducting operations over Perth Water on the Swan River, that included low-level passes of the Langley Park foreshore.
After conducting two passes in company, both aircraft departed the display area. The pilot of CQA subsequently requested and received approval to conduct a third pass, and returned to the display area without the Cessna Caravan. During positioning for the third pass, the aircraft departed controlled flight and collided with the water. The pilot and passenger were fatally injured.
What the ATSB found
The ATSB found that the aircraft aerodynamically stalled during a positioning turn for the third pass, resulting in the collision with shallow water. The manner in which the pilot returned to the display area after the second pass was not in accordance with the display procedures and increased the risk of mishandling the aircraft in an area of relatively close proximity to the public. The pilot’s decision to carry a passenger was also contrary to the requirements of the display instrument and increased the severity of the outcome.
Finally, a safety issue was identified with the current regulatory framework for air display approval and oversight.
What's been done as a result
The Civil Aviation Safety Authority had independently published a revised manual of guidance for air displays in September 2017. The document provided further detail on the key roles and their responsibilities and introduced a requirement to conduct a risk assessment as part of the application process. In April 2018, CASA updated the associated participant form, which was expanded to assist pilots with their display preparation and included a requirement to identify and provide justification for any additional persons on board display aircraft. The form also included a section to provide additional assurance around completion of the display coordinator’s responsibilities.
Finally, the ATSB has issued a safety recommendation to CASA to undertake further work to enhance their tools and guidance for air display approval and oversight, and procedures to ensure the suitability of those responsible for organising, coordinating and participating in air displays.
Safety message
Air displays are activities with inherent and unique risks that pilots, the organisers and the regulators all have responsibilities in addressing. It is important that holders of these key positions have a thorough understanding of their role and responsibilities, to ensure adequate completion of safety critical tasks. Having well-defined, transparent and consistent processes for planning and approval of air displays will assist in identifying risks and implementing effective mitigation strategies.
In addition to complying with regulations, pilots can limit their risk exposure by only participating in displays that are within their own and their aircraft’s capabilities and limitations, and not undertake any impromptu manoeuvres that have not been planned or practiced.
These steps combined will provide greater safety assurance for participants, spectators and the general public.
VH-CQA
Source: Flightaware.com
The occurrence
On 26 January 2017, the pilot of a Grumman American Aviation Corp G-73 amphibian aircraft, registered VH‑CQA (CQA), was preparing to participate in an air display as part of the City of Perth Australia Day Skyworks (Skyworks) event.
The pilot of CQA and a passenger arrived at Serpentine Airfield, 48 km south of Perth (Figure 1), at about 1500 Western Standard Time,[1] to prepare the aircraft for flight. The pilot was reported to have used his mobile phone to discuss aircraft performance with another individual and subsequently unloaded some equipment to reduce the aircraft’s weight. At about 1625, once the pilot had confirmed via phone the take-off calculations for the runway length and local temperature of about 42˚C, he and his passenger, who did not have any pilot qualifications, boarded CQA.
The pilot was in the left seat and the passenger in the right seat. CQA departed from runway 23 and tracked out towards the coast. The pilot of another aircraft returning to Serpentine Airfield observed CQA’s departure and described it as a ‘long and slow climb’, which they surmised was due to a combination of the high ambient temperature and the aircraft’s inherent performance.
The pilot of CQA planned on flying ‘in company’ (see the section titled Procedure for fly‑bys) with a Cessna Aircraft Company C208 ‘Caravan’ amphibian, registered VH-MOX (MOX) during the air display. The pilot of MOX received a text message from CQA’s pilot, advising that he would not be landing at Jandakot Airport as previously discussed and requested that they meet up overhead the agreed alternative location of Cockburn Sound (Figure 1). MOX departed from Jandakot at about 1645 and met up with CQA over Cockburn Sound.
Upon meeting up, the pilot of CQA assessed that MOX’s speed was too high for the two aircraft to travel together and requested that the Caravan pilot slow his aircraft down. The pilot of MOX agreed to slow down with a request that CQA ‘didn’t get too close’. Both aircraft then flew the prescribed route to Perth Water, the location of the air display. The weather was fine with a recorded wind of about 20 km/h from the south-west and a temperature of about 39°C.
Figure 1: CQA and MOX flight path
Source: Google Earth, modified by ATSB
Once approved to enter the display area, CQA followed MOX via the prescribed inbound route to the north of Perth city in order to conduct a fly-by parallel to the Langley Park foreshore in a westerly direction (Figure 2). MOX conducted a splash‑and‑go[2] in front of Langley Park while CQA followed at about 200 ft above the water. The delay associated with MOX’s splash-and-go resulted in the separation between MOX and CQA reducing. MOX lifted from the water surface, entered a climbing turn and conducted a left orbit[3] within the confines of Perth Water to reposition for a second pass of Langley Park.
Flight data and video footage showed that CQA took longer to initiate the left orbit and subsequently flew at about 500 ft over the built-up area of the South Perth peninsula that connects to the Narrows Bridge, at the western end of Perth Water. CQA then descended to about 200 ft over the south of Perth Water while repositioning for a second pass.
Figure 2: CQA air display flight track, showing the first pass in yellow, the second in magenta and the third in red
Source: Google Earth, modified by the ATSB
When MOX conducted its second splash-and-go in front of Langley Park, CQA was about half an orbit behind, flying in an easterly direction along South Perth foreshore. Following completion of the splash‑and‑go, the pilot of MOX climbed over the Narrows Bridge to about 1,000 ft for the return flight to Jandakot. CQA’s second fly-by of Langley Park was lower than the first, descending to just above the water surface, before a climb was also initiated to clear the Narrows Bridge.
On departure from Perth Water, the pilot of MOX transmitted on the display frequency that he was exiting the display area and returning to Jandakot Airport. CQA flew over the Narrows Bridge and initially followed MOX toward Jandakot, during which time the pilot requested approval to conduct a third pass. This request was authorised via radio by the ‘Ringmaster’,[4] but as the pilot of CQA did not hear the authorisation, MOX re‑transmitted the approval to CQA, while continuing with their own departure. CQA then conducted a left turn and returned directly to Perth Water, at about 300-400 ft over the built-up area and moored spectator boats.
CQA flew in an easterly direction, parallel with the South Perth foreshore, before commencing a left turn towards Langley Park to position for the third pass. The aircraft was at a similar altitude to the first orbit at the commencement of the turn, but was slower and positioned further towards the middle of Perth Water (Figure 3). Video and still imagery recorded that the wing flaps were in the retracted position. The left turn was tighter than that of the first orbit and during that turn, CQA rolled left and pitched nose-down, consistent with an aerodynamic stall[5] (Figure 4). The aircraft collided with the water and was destroyed. The pilot and passenger were fatally injured.
Immediately after the accident, the remainder of the air display was cancelled, followed shortly after by cancellation of the entire Skyworks event.
Figure 3: CQA's pass along South Perth, just prior to the final left turn
Source: David Roses
Figure 4: CQA just prior to the collision with water (looking north)
The pilot held a Private Pilot (Aeroplane) Licence issued in July 1994, and a current Class 2 Aviation Medical Certificate. His endorsements included floating hull, manual propeller pitch control and retractable undercarriage, and he held single- and multi-engine ratings. The pilot completed his floating hull endorsement in October 2011 on a LA-4-200 Lake Buccaneer Amphibian. In 2012, he completed about 18 hours of flight training[6] in the Grumman American Aviation Corp G-73 Mallard (Mallard) in the United States, under his Federal Aviation Administration (FAA) licence.
The pilot accrued about 21 hours on VH-CQA (CQA) between 6 and 13 January 2017. Prior to that, he had not flown any aircraft since 29 August 2016. The pilot conducted no further flights until 26 January 2017. At the time of the occurrence, the pilot’s logbook indicated that he had 625 hours flying experience, with about 180 hours in the Mallard.
The pilot had accrued 136 water landings, of which 84 were completed over the two days of his floating hull endorsement. The pilot’s Mallard water landing experience consisted of 37 landings during dual training and 11 while solo. The pilot’s most recent water landing (which was in CQA) was conducted on 28 February 2016.
Post‑mortem examination and toxicological analysis of the pilot and passenger did not identify anything that may have contributed to the accident.
Mallard rating and flight reviews
The pilot’s Mallard training in the United States, was completed on 25 May 2012 and was conducted on the same aircraft that was later registered as VH-CQA (see the section titled Aircraft information). The pilot’s log book was endorsed as ‘training completed’ and ‘unrestricted land and sea use of the G73’ and he commenced flying the Mallard solo, in Australia on 30 July 2012.
Due to an administrative error during conversion of the pilot’s United States flight crew licence, his Civil Aviation Safety Regulations (CASR) Part 61 licence was not issued with a G-73 rating. This was identified by the Civil Aviation Safety Authority (CASA) during the air display application process. The pilot applied for the G-73 rating on 19 January 2017 and his licence was reissued with the type rating on 24 January 2017.
CASA Instrument 186/14 published on 25 August 2014, introduced prescribed aircraft, ratings and variants for the CASR Part 61 licencing system. On 23 December 2014, CASA published Prescription of aircraft and ratings– CASR Part 61, identifying those aircraft considered sufficiently complex or having performance or handling techniques that warranted initial specific training and per-type flight reviews. Schedule 6 of this document identified the Grumman G‑73 Mallard as a type-rated aircraft.
The pilot’s most recent biennial flight review was conducted in April 2016 in a Piper PA-30 Twin Comanche. The flight review prior to that (April 2014) was also conducted in the PA-30. An exemption to CASR Part 61, EX97/16, allowed for a multi-engine aeroplane class rating flight review to satisfy the flight review requirement for a type-rated multi-engine operation. The pilot therefore satisfied the flight review requirement to fly the Mallard, but had not had a review in the aircraft type since his endorsement.
Despite the exemption, all pilots were subject to the CASR 61.385 ‘general competency rule’, which indicated that a pilot is only authorised to fly an aircraft if they are competent to the standards mentioned in the CASR Part 61 Manual of Standards. Outside of the requirement for flight reviews, the pilot was responsible for ensuring his competence to fly the aircraft.
The instructor who provided the pilot’s floating hull endorsement training flew with him again in April 2015, this time in the Mallard. He recalled the pilot as being ‘generally pretty good’, but that he ‘wasn’t quite up to speed with the aeroplane’ and suggested that this may have been due to the pilot’s irregular flying.
Air display experience
The pilot participated in several air displays whilst flying CQA, including the:
Great Eastern Fly-In (GEFI) events at Evans Head Aerodrome in New South Wales in 2015, 2016 and 2017.
Brisbane Valley Air Show (BVAS) at Watts Bridge Memorial Airfield, Queensland in 2016.
The programs for these events indicated that the pilot demonstrated a ‘handling display’. Review of video footage showed that the displays included one or more straight and level fly-bys with repositioning turns for return passes.
The pilot’s application to take part in the Perth air display described the proposed display as ‘same display as used previously at GEFI and BVAS, minimum height 300 ft, no aerobatic manoeuvres, multiple passes, no ‘dirty pass’,[7] all within normal operating manual’.
Familiarity with the Perth Water air display area
On 13 January 2017, during CQA’s repositioning from New South Wales to Western Australia, the pilot undertook a flight from Esperance to the north of the Perth metropolitan area and then tracked south along the coast before turning inland, toward Perth city. During this time, the aircraft flew in an easterly direction along the Langley Park foreshore at about 1,000 ft, before turning right prior to the Causeway Bridge (Figure 6). CQA was then flown in a westerly direction toward the south Perth peninsula, where the aircraft tracked toward Fremantle, then down the coast toward Serpentine Airfield. The pilot did not fly CQA again until the air display on 26 January 2017.
Aircraft information
The Grumman American Aviation Corp G-73 Mallard is a high-wing, medium-sized amphibious aircraft[8] with under-wing floats, retractable landing gear and two-step hull (Figure 5). It was powered by twin Pratt & Whitney R-1340 Wasp radial engines. The Mallard was designed for regional airline operations with two pilots and ten passengers. Fifty-nine aircraft were built between 1946 and 1951.
Mallard serial number J-35 was built in 1948 in the United States and was first registered in Indonesia that same year. In 1976, the aircraft was relocated to the United States and operated there before the occurrence pilot purchased it and transferred it to Australia in July 2012. The aircraft was then based at Evans Head Airfield, New South Wales.
Figure 5: VH-CQA
Source: David Roses
The aircraft flew in Australia under its United States registration until it was re‑registered as VH‑CQA (CQA) in July 2013. In August 2013, CQA was issued with a Special Certificate of Airworthiness in the Experimental – Exhibition category with defined operating requirements. This included that any passengers were to be made aware that the design, manufacture and airworthiness of the aircraft was not required to meet any standard recognised by CASA and that flight in the aircraft was at their own risk. In addition, warning placards detailing this information were to be placed in full view of all passengers.
Flight characteristics and performance considerations
The ATSB sought the input of two experienced Mallard pilots and a CASA-authorised flight analyst in order to gain appreciation of the flight characteristics of the Mallard and its performance considerations. It was commented that the Mallard could easily be operated by one pilot. However, it was also mentioned that because it has a constant-angle, high performance wing[9] it ‘requires more care than with a wing that provides more lift at a slower speed’, particularly as a stall can result in the aircraft going ‘straight onto its back’.
Maintenance history
CQA was maintained in accordance with a CASA-authorised System of Maintenance (SOM). This SOM was effective as at May 2013 and the aircraft was required to undergo a conditional ‘periodic’ inspection every 12 months or 100 hours, whichever came first. CQA was maintained by a CASA-authorised maintenance provider, who conducted a periodic inspection and issued the current maintenance release, on 6 January 2017. At the time of the accident, the aircraft had accumulated about 22 hours since that periodic inspection and had a total time in service of 7,336 hours.
As CQA was reportedly being relocated to Western Australia, the maintainer released the maintenance log books to the pilot. However, they could not be located following the accident and the maintenance history could therefore not be reviewed by the ATSB. Information from CASA and other sources did not identify evidence of any previous accidents involving the aircraft.
An installed autopilot was removed from CQA as part of Supplemental Type Certificate SA635SO, prior to its delivery to Australia. Removal of that equipment reduced the maximum certificated take-off weight to 5,700 kg. The aircraft flight manual authorised the G‑73 for single-pilot operation[10] and CQA’s instrument panel was set up for left-seat, single-pilot operations.
CQA was not fitted with a stall warning device[11] and there was no requirement for one.
VH-MOX and flight crew information
VH-MOX (MOX) was a Cessna Aircraft Company 208 ‘Caravan’ that was manufactured in 1993 and first registered in Australia in 1994. The Caravan is an all-metal, high-wing aircraft that is powered by a single Pratt & Whitney PT6A turboprop. MOX was fitted with floats with retractable landing gear to allow for land and sea operations. The Caravan had a maximum take‑off weight of about 3,600 kg.
The flight crew of MOX consisted of the pilot in command (PIC), in the left seat, and an observer, in the right seat. The PIC held a current instrument and Grade 1 instructor rating and had extensive float experience operating Caravans. The PIC also had commercial Caravan operations experience within Perth Water and had operated the aircraft there in the week prior to the air display. In addition, the PIC had previous experience participating in the Perth Air Display.
The observer was a pilot with significant experience in float planes and floating hull aircraft, at Perth Water and other locations. He held a Grade 1 instructor rating and had over 27,000 hours flying experience. In addition, he had previous air display experience in light aircraft. Both pilots had low-level endorsements, with recent experience, and had flown with each other previously.
Meteorological information and water conditions
The Bureau of Meteorology reported the weather conditions for 26 January 2017 were ‘fine, very hot and sunny’ with temperatures reaching 42˚C in the Perth area[12] during the day. Perth Airport records for 1500 indicated the temperature was 41.5˚C with a relative humidity of 9 per cent. Wind speed and direction recordings from nearby Melville Water indicated a wind speed of about 11 knots from 226˚ (20 km/h from the south‑west). Pilots in the air display described the water condition as ‘ideal’, not glassy, with small ripples to assist with depth perception and wind direction identification.
The sun was low in the sky to the west and was unlikely to have affected the pilot’s visibility immediately prior to the collision, when the aircraft was flying east and then turning north.
Recorded data
Analysis of available track data (as depicted in Figure 2) found that the Mallard’s speed on entry to the accident turn was approximately 10 kt slower than at the equivalent point in the previous orbit and within around 10 kt of the aircraft’s stall speed for a coordinated turn at an estimated 30° angle of bank at the commencement of the turn.
Site and wreckage information
CQA collided with water on the Swan River, in a shallow section, approximately mid-way between the Langley Park and South Perth foreshores and about 700 m west from The Causeway. A navigable channel had been dredged parallel with the Langley Park foreshore, the remainder of Perth Water was relatively shallow, with a layer of silt. The mostly‑submerged wreckage was recovered and transported by barge to a nearby secure facility for technical examination.
Damage to the aircraft was consistent with the observed collision with water in a steep nose-down attitude and subsequent contact with terrain, about 1.5 m below the surface. Examination of the wreckage did not identify any evidence of in-flight break‑up, component failure or other anomalies that may have contributed to the collision with terrain, or that would have prevented the engines and propellers from operating normally. This was consistent with witness reports, images and video of the aircraft during the display.
Conduct of the air display
Overview
The City of Perth (CoP) managed the Australia Day Skyworks (Skyworks), which consisted of a series of events on 26 January each year, culminating in a fireworks display from barges moored in the centre of Perth Water (Figure 6). Perth Water is located on the Swan River between Langley Park and the South Perth shoreline, the Narrows Bridge in the west and Causeway in the east. Events included various activities on the Langley Park foreshore and the South Perth foreshore, which was coordinated by the City of South Perth. Water-based events and the air display were managed on behalf of CoP by a contracted events management company. Up to 300,000 people attended each year.
The air display had been a part of the Australia Day activities since 1993. The event was originally organised by an individual, then through the Royal Aero Club of Western Australia, before being incorporated into the CoP’s overall management of the event.
The air display was scheduled to run from 1530 until 2000, before the commencement of the fireworks display. The programme consisted of fly-bys (small vintage aircraft, like Tiger Moths, through to a medium-sized Fokker 100 jet), individual and group aerobatics, banner/flag-towing, aerial displays from water-bombing aircraft and float plane ‘splash-and-go’s’. The participating pilots were mostly volunteers, many of whom had been associated with the event for many years. Several of the pilots also participated in multiple displays on the day.
Figure 6: Perth Water
Source: Google Earth, modified by ATSB
Airspace
Perth Water is located about 10 km west‑south‑west of Perth Airport, in class C airspace. A temporary danger area (TDA)[13] ‘Area ALPHA’ (Figure 7) was established by Airservices Australia for the duration of the air display, from surface up to 1,500 ft AMSL.[14] This allowed air display aircraft to operate in Perth Water without the need for specific air traffic control (ATC) clearance. A central point of contact ‑ the Ringmaster ‑ was required to maintain two-way communication with Perth ATC and coordinate aircraft access into Area ALPHA on a specified frequency. Standard airspace procedures were required for operations outside of Area ALPHA.
Figure 7: Google Earth image showing approximate location of Perth Water within Area ALPHA.
Source: Google Earth, modified by ATSB
Air display program and procedures
The CASA-approved air display program documented all participating aircraft, flight crew and routines for the display. Where a routine involved multiple aircraft, one aircraft was designated the ‘lead’ aircraft and would conduct all radio communications on behalf of the group. Each display was scheduled in 10‑15 minute time slots. The display program was often similar to the year before, depending on availability of aircraft. All pilots taking part in the air display were provided with briefing notes, which included a copy of the CASA approval, airspace procedures, air display program and standard display procedures.
Inbound, holding and outbound tracking
The procedures for approach and departure from the display area were detailed in ‘display procedure B2’ (Figure 8). Once aircraft had entered Area ALPHA they were to track toward the holding area XRAY at an altitude of 1,500 ft (D1 INBOUND OUTBOUND HOLDING). If holding was required, aircraft would perform right orbits until they were given clearance by the Ringmaster to track inbound to Perth Water. Unique displays, including aerobatics, entered Perth Water in accordance with their documented routine.
For all non-aerobatic aircraft, the standard inbound route to the display area (Perth Water) was to fly over Kings Park then Northbridge (to the north of Perth City) and via the Graham Farmer freeway toward the East Perth power station (D2 INBOUND DISPLAY AREA). Aircraft descended to 1,000 ft while flying over the Swan River toward the Causeway and Perth Water. Departure from the display area was via the Swan River at 1,000 ft toward Fremantle, until clear of Area ALPHA.
Figure 8: Extract of the CASA‑authorised B2 display procedure supplied to all participants
Source: CASA
Procedure for fly-bys
Fly-bys (procedure D3, Figure 9) were to be performed by groups of aircraft flying ‘in formation’ or ‘in company’. The program noted that ‘formation rated and current pilots [are to] only [fly] in formation groups up to maximum of 6. Other aircraft [including those operating in company] were to maintain 600 metre separation between each other’.
Figure 9: Extract from the ‘display procedures – B2’ diagrams, showing the arrow that indicates the direction and location of the float plane landing area
Source: CASA
Following the standard approach and departure procedure, aircraft conducting fly-bys were to descend from 1,000 ft to not below 500 ft over the channel of water between the pyrotechnic barges (red rectangle, Figure 9) and Langley Park foreshore. The aircraft were to depart over the Narrows Bridge (Figure 6) and track over the Swan River at 1,000 ft, back toward Jandakot Airport.
If additional fly-bys were approved by the Ringmaster, there were two options to re-enter the D2 ’inbound display area’ procedure:
aircraft could turn right before Kings Park and fly along the freeway on climb to 1,500 ft and re‑join the D2 procedure at the western end of Northbridge, or;
from the Narrows Bridge they could track along the Swan River and fly over Kings Park on climb to 1,500 ft, before re-joining the D2 procedure at Northbridge.
The standard D3 procedure was to be followed for the remainder of any additional fly-bys. Between one and three fly-bys, per display, had been the standard in preceding years. Fly-bys and multiple passes were not specifically detailed with respect to the float plane procedure.
Procedure for float planes
Float planes had been part of the air display in the past, but not every year. Previous float plane displays had included the Cessna C208 Caravan, a Cessna 206 and a Lake Aircraft LA-4-200 Buccaneer.[15] The display coordinator (DC)[16] advised that float planes were added to the air display about 10 years prior to this accident. A representative from CASA observed him demonstrate the intended display in a Cessna 206, before they were approved for inclusion in the display program. The C208 Caravan was the most frequently used aircraft type for this display.
Within Perth Water, the float planes were permitted to descend to the water surface. On some occasions they had landed and back-tracked before turning around and taking off. However, it was reported that when conditions were suitable, float planes were expected to conduct a splash‑and‑go, remaining on the step.[17] The C208 Caravan float plane procedure submitted to CASA for 2015 and 2017 was essentially the same and is shown in Figure 10.[18]
Figure 10: Float plane procedure approved by CASA in 2015 and 2017
Source: CASA
A procedure for the Mallard was added to the float plane procedure for the 2017 air display and included ‘touching the water the same as above [the C 208] but without getting off the step’.
Both the floatplane and flying boat procedures contained a contingency to conduct a missed approach while remaining in the display area if water and wind conditions were not suitable. Both procedures also made reference to ’approach…per standard bridge clearance procedure’. There was no reference to what this procedure was, but it was assumed by the ATSB to be the standard approach and departure (B2) procedure.
The B2 display procedure included the ‘D6 Floatplane Landing’ (Figure 9) location at the northern edge of the display box.
Actual conduct of the float plane display
When the float plane display was first introduced, the aircraft would usually land, back-track and then take off. While not documented, the sequence was subsequently altered to a splash-and-go, followed by the left orbit. That variation had reportedly been in place for a number of years.
The float plane procedure in practice was therefore to approach from behind the city to enter Perth Water, conduct a low pass (or splash‑and‑go) at the northern edge of the display box, followed by a left orbit within the confines of Perth Water, before conducting a second pass along the Langley Park foreshore. The float planes would then depart as per the standard procedure or conduct a second left orbit if they were going to do a third pass/splash‑and‑go.
This sequence was consistent with the display briefing given the night before the activity, where the float plane display was described by the DC as follows:
The float planes… will be doing their touch and go…but they won’t be landing fully. If anything they [are] just kissing the water and then do an orbit and then another one and then [depart].
Further, video footage of the briefing showed the DC indicating left orbits on the projected map at this time.
CASA’s understanding of the float plane display sequences
CASA personnel who approved the display advised that they were not aware left orbits within the confines of Perth Water were being conducted during the float plane display. They reported having an understanding that:
the float planes would conduct the standard approach from behind the city
perform one low pass, or splash-and-go
depart via the standard procedure.
They further stated that had they known left orbits were being conducted, they would not have approved a ‘turn into that area in a Caravan, let alone a much larger aircraft’.
The DC advised he had not mentioned the left orbits to CASA as they had never specifically enquired about the float plane sequence. However, CASA staff were present for the briefing conducted the night before the activity, in which the conduct of orbits was described.
Operation within Perth Water
The ATSB spoke with Caravan and Buccaneer float plane pilots who had experience operating within Perth Water and were therefore familiar with the display area. They noted that their aircraft did not have a lot of room to manoeuvre and described Perth Water as a ‘confined’, ‘constricted’ and ‘very tight operating area’.
Air display conditions for conducting the display in Perth Water were captured in the display instrument, and included that:
Non-aerobatic display aircraft are not to be operated below 1.3 times the stall speed for the aircraft’s configuration.
…display aircraft will pass no closer than 200 metres horizontally from spectators. Aircraft below 1500 feet AGL shall not track or manoeuvre directly towards spectators within a horizontal distance of 500 metres.
For aircraft operated by pilots holding a low-flying approval, the demonstration may be conducted with the following manoeuvring limitations:
a) Between 50-200 feet AGL – wings level only
b) Between 200-300 feet AGL – up to 30 degrees angle of bank
c) Between 300-500 feet AGL – up to 60 degrees angle of bank
Despite the differences in understanding of the intended display between CASA and the display participants, and the stated effect on the display approval, the ATSB determined that it was possible to conduct orbits in the Mallard, while adhering to the display conditions, however there was little room for error. A similar conclusion was reached by CASA in their post-occurrence regulatory safety review.
However, following review of the draft investigation report, CASA advised that the conduct of orbits within Perth Water could not be conducted in compliance with Civil Aviation Regulation (CAR) 157. Despite this, the ATSB noted that CASA did approve the conduct of essentially identical manoeuvres in the form of a ‘…go around whilst remaining in the display area’, per the display procedure.
Approval of VH-CQA in the air display
The DC met the pilot of CQA in late 2016. In early 2017, when he became aware the aircraft was coming to Western Australia, he invited the pilot to participate in the air display. In January 2017, leading up to the air display, the following key interactions to facilitate participation of the aircraft and pilot occurred:
In an email to CASA on 4 January that included documents for the air display application, the DC mentioned the possibility of CQA being involved in the display. The display procedures submitted in this email included one for ‘flying boat’. He also provided details for several display pilots, including the pilot of CQA.
On 11 January, the DC advised CASA via email that another float plane had been added to the program to fly with CQA. However, a revised procedure detailing this new aircraft was not included in this email.[19]
On 12 January, CASA asked the DC if the pilot of CQA was going to get an opportunity to practice prior to the event. He replied that it would be the same as ‘all other displays where pilots will prepare appropriately’, and that he would meet with the pilot of CQA when he arrived in Perth. CASA then requested the pilot of CQA provide a statement in relation to the water depth in the proposed landing area, for the appropriate date and time of the event. The DC replied there would likely be a water depth of about 1 m.
On 16 January, the DC sent an email to the pilot of CQA where he offered to be ‘co-pilot’ during the display, to ‘help with the radio and procedure’.
In an email to CASA on 17 January, the DC indicated that he had spoken with the pilot of CQA and agreed that he would only do a splash-and-go and that the aircraft would not get off the step.
During a phone call on 19 January, the DC was advised by CASA that the pilot of CQA would not be able to participate in the air display without the required G-73 type rating being endorsed on his licence. The DC advised the pilot of CQA of the issue with the type rating via email and that CASA had agreed to wait until midday 23 January when, if no evidence of this type rating was provided, CQA would be withdrawn from the program.
About a week before the air display, the DC arranged with CASA for MOX to be included in the display and submitted details for the pilot and advised that he was still waiting for confirmation that CQA could participate. The email advised that the pilot of MOX had been in the display three years previous and had ‘done this very sequence’, described as being ‘fly by + touch and go on water’.
On the evening of 23 January, the DC submitted a revised float plane display sequence showing details solely for the Caravan. The Instrument (the approval - the term Instrument is discussed in the section CASA approval and oversight of air displays) was sent to the DC at 1940 that evening.
On the afternoon of 24 January, the DC emailed CASA with documents showing that CQA’s pilot now held the required G-73 type rating and an ‘authority to fly letter’ from CASA. He also requested that CQA now be included in the display. He also submitted the float plane display sequence including the Mallard and the Caravan and a revised program, which now showed CQA and MOX. In his email to CASA, the DC also stated that as a member of the CASA team had reportedly had a concern about the ‘first time [participation of a new pilot and aircraft type]’, he would ‘go along to be of support [to the pilot] for the procedure which should mitigate against that concern’. Revision 2 of the Instrument was issued by CASA that evening.
Risk mitigation
CASA personnel reported that they approved the inclusion of CQA on the basis of having the DC on board, to mitigate against the risk associated with having a new pilot and aircraft type involved in the display. CASA’s documented reason for allowing CQA to participate in the display referred to the email received from the DC on 24 January (detailed above), indicating that he would be on board.
The DC reported that he originally offered to be on board to assist the pilot with any procedural aspects associated with his first time in the display. However, he indicated that having CQA follow MOX for the display effectively mitigated that concern. He also indicated that his offer to be on board CQA was not acknowledged by CASA and there was no indication that this was their expectation. Therefore, he believed his presence on board was not a requirement. Additionally, the pilot elected to depart from Serpentine Airfield, rather than the original Jandakot Airport departure point. As the DC was a participant in five displays that day, he would not have had the time to travel to Serpentine in order to be on board.
As part of their post-occurrence regulatory safety review (see the section titled CASA approval and oversight of air displays section) of the lead-up and conduct of the air display, CASA identified that despite their expectation that the DC would be on board CQA, they had not specifically advised the DC of this, nor was this requirement included in the Instrument of approval. CASA also did not advise the pilot of CQA that the DC being on board was a requirement for his inclusion.
Pre-display briefing and flight planning
The CASA air display guidance manual (see the section titled CASA approval process for air displays) detailed that a written brief of the flying program should be circulated in advance of the air display, to pilots and those in other critical roles. In addition, ‘a formal verbal briefing should be given on the day of the display and at any rehearsal, and all participants, where possible, must attend’. Those not able to attend were to be verbally briefed separately. The manual listed the minimum items that were to be covered in the briefing.
The Skyworks pre-display briefing was held at Jandakot Airport the night before the event. All air display participants were required to sign Form 695 Participant signature sheet, acknowledging that they have read the CASA approval for the air display and would operate their aircraft in accordance with the terms of the approval. The briefing was conducted by the DC in a large cafeteria-style room, with participants seated at various small tables. The Ringmaster and CASA also addressed the participants. The event was video recorded by the City of Perth and the footage[20] was reviewed by the ATSB. Participants were seen reviewing copies of the written brief, which had been provided to them at the commencement of the briefing.
The briefing included a discussion of the display area, air space, radio communications and standard approach, holding and departure procedures. As detailed previously, the extent of the float plane-specific brief was, ‘the float planes… will be doing their touch and go…but they won’t be landing fully. If anything they [are] just kissing the water and then do an orbit and then another one and then [depart]’. The DC also discussed the importance of aircraft serviceability, the anticipated weather conditions, considerations about personal fatigue and to ‘have your own risk management’. He also emphasised that they were the lead-up to the main event and there was ‘no pressure to do anything special’, ‘just do everything as you normally do, don’t do anything different’ and to ‘have your own limitations’. The DC reported that separate ‘formation’ briefs were conducted for participating pilots on the morning of the air display, prior to departure from Jandakot Airport.
The pilot of CQA attended the briefing, where he first met the pilot and observer of MOX. The pilot of MOX reported that:
he and the pilot of CQA discussed airspeeds, who would lead and who would be on board CQA
it was arranged that the two aircraft would meet at Jandakot Airport (where CQA could refuel and/or collect the DC) or overhead Cockburn Sound (if CQA flew directly from Serpentine Airfield)
MOX would be the lead aircraft, handle the radio calls and general procedures, so that CQA could follow.
The pilot of MOX reported that he did not have any expectations of CQA’s pilot, other than CQA would follow MOX. He recalled that the pilot of CQA had suggested he would not touch the water, but conduct a low overshoot. On the day of the display, the pilot of MOX received a text message from the pilot of CQA at about 1515, advising he would meet MOX overhead Cockburn Sound.
Carriage of passengers during the air display
Civil Aviation Regulation (CAR) 2 Interpretation defines a ‘crew member’ as a person assigned by an operator for duty on an aircraft during flight time and ‘operating crew’ as any person who:
• is on board an aircraft with the consent of the operator of the aircraft; and
• has duties in relation to the flying or safety of the aircraft.
CASR Dictionary – Part 1 – Definitions describe the following roles:
Flight crew member means a crew member who is a pilot or flight engineer assigned to carry out duties essential to the operation of an aircraft during flight time.
Passenger, in relation to an aircraft, means a person:
(a) who:
(i) intends to travel on a particular flight on the aircraft; or
(ii) is on board the aircraft for a flight; or
(iii) has disembarked from the aircraft following a flight; and
(b) who is not a member of the crew of the aircraft for the flight.
Under Civil Aviation Order 29.4 Air Displays, one of the conditions of approval to conduct an air display is that ‘passengers shall not be carried for hire or reward during any part of the air display except where specifically approved as part of the program’. While this did not exclude the carriage of passengers for no compensation, the CASA instrument of approval for the 2017 Skyworks air display was more explicit, stating that ‘passengers shall not be carried in display aircraft and only aircrew essential to the operation of the aircraft are to be carried’. Similarly, the following statements were included in the Flight Crew section of the air display manual:
No persons other than operating crew may be on board a civil aircraft during the air display unless the prior written permission from CASA has been obtained.
The responsibility for ensuring that an aircraft is operated in accordance with its Certificate of Airworthiness, Permit to Fly and Air Display Approval rests with the pilot in command. This does not absolve the Display Organiser from the responsibility to take such action as is necessary should a display aircraft deviate from the bounds of any approval or operate in an unsafe manner.
In addition to the regulatory considerations above, as part of the pre-display briefing the DC reinforced that ‘you’re not allowed to carry passengers but you are allowed to carry operational crews’.
During discussions following the pre‑display briefing conducted on 25 January 2017, the DC was made aware that the pilot of CQA intended to have an additional person on board, in the right front seat. The pilot had mentioned to several people that it was necessary for this person to be on board CQA to assist in the case of needing to manually deploy the main landing gear. The Mallard’s flight manual did not include this method for releasing the main gear and other Mallard pilots reported being unaware of it.
This reasoning was also raised by the pilot when questioned by CASA officers after they witnessed two people disembark the aircraft during CQA’s participation at the Great Eastern Fly-In events at Evans Head Aerodrome, New South Wales on 7‑8 January 2017. The outcome of that conversation was that the CASA officers informed the pilot that his passenger did not meet the definition of essential crew.
The CASA officers that participated in the discussion at Evans Head were from the sport aviation office and were not aware of the pilot’s application to participate in the Perth Air Display. The Perth office was similarly unaware of the discussion that had taken place at the Evans Head event when they assessed the pilot’s application for the Perth display.
The pilot’s logbook indicated that his passenger had flown on CQA several times, between 6‑13 January 2017 and had a total time on board CQA of about 19 hours. While it was reported that the passenger was interested in flying training, information received from CASA and the National Transportation Safety Committee (NTSC), Indonesia found that she had not registered with either organisation and did not hold a flight crew licence.
It was also reported that the pilot had invited another person to be on board during the Skyworks display. However, the pilot’s decision to minimise the weight of the aircraft due to the temperature on the day, prior to departure from Serpentine Airfield, resulted in that person not being on the accident flight.
Following a recommendation from their regulatory safety review conducted after this accident, CASA published a revised Form 697 Pilot or essential crew details in April 2018. This expanded form added a checklist of considerations for display pilots in relation to their intended display. Sections were also included to allow for identification and reasons for the requirement of additional crew and a DC checklist to ensure consistency in the application. In addition, this form was now required to be signed by the pilot, crew (if applicable) and the DC.
Air display roles and responsibilities
Documented roles and responsibilities
CASA’s Air Display: Safety and Administrative Arrangements manual (air display manual) provided guidance on the minimum safety and administrative procedures necessary to run an air display. The manual included a list of key personnel and their responsibilities, most notably, that of the Display Organiser, Display Coordinator and flight crew (Table 1).
Table 1: CASA Air Display Administration and Procedure Manual[21] terminology of air display roles
Display Organiser (DO)
The air display ‘organising body must appoint one person as the DO to assume overall responsibility’. This person is also expected to be ‘personally familiar with each pilots’ display routine and ensure that it complies with the safety criteria’. They are responsible for the planning and display management, including:
appointment of DC, flying display committee, officials and flight crew
site assessment
marking of the display axis
pre-display briefing
document checks
pilots’ display programs (both normal and weather-restricted programs).
Where the DO does not have ‘considerable aviation experience’, they are to appoint a ‘suitably qualified person, preferably with display experience, as the DC.
Display Coordinator (DC)
The DC is ‘sometimes referred to as the Ringmaster because he/she controls the actual flying program’.
The DC’s responsibilities included:
flying discipline in general
compilation, approval and modification of individual flying routines
the overall flying program
cancellation or modification of the flying program in the event of unsuitable weather or other such conditions.
‘It is strongly recommended that, before being appointed as a DC, the DC should have had the experience of being an Assistant DC or being in a similar subordinate role in at least one Air Display of similar complexity.’
Flight Crew
The pilot in command’s responsibilities included:
ensuring the aircraft is operated in accordance with its certificate of airworthiness and the air display approval
planning their flying sequence to maintain minimum separation distance from the crowd line.
During the pre-display briefing, the pilots were to be reminded ‘that flying over the crowd, car park or any public enclosure is prohibited and any turns towards these areas must be completed without infringing the safety buffer between the display axis and the crowd line’.
The CASA-issued instrument granting approval for the 2017 air display assigned the City of Perth to the role of ‘Display Operator’ and separate individuals to the roles of DC and Ringmaster. The instrument did not assign a DO.
The role of Display Operator was not defined in the air display manual, however they, along with the DC, had a responsibility via the instrument to ensure that the display was conducted in accordance with the relevant legislation.
Recognising the discrepancy between the roles defined in the air display manual and the instrument, the role titles identified in the CASA‑issued Perth air display instrument are used throughout this report for consistency.
Display Coordinator
During the 2017 display organisation and approval, the DC carried out some of the responsibilities of that role, as well as that of the DO, per the air display manual. When interviewed by the ATSB, members of the CASA team referred to the same individual as both the DO and DC. It was noted that this was possible in accordance with the manual.
The DC held an Air Transport Pilot (Aeroplane) Licence and a Commercial Pilot (Helicopter) Licence, for single- and multi-engine aeroplanes and single‑engine helicopters. He held multiple design feature endorsements including floating hull and float plane. The DC was endorsed for aerobatic flight activities and held low-level ratings for both aeroplanes and helicopters.
The DC had been involved as a pilot in the Perth Air Display since its inception and over time voluntarily took on various roles with respect to planning, procedures and approvals. He was directly involved in developing the display program and conducting the pre-flight brief, typically the night before the event. He advised that on the day of 26 January each year, ‘I’m just a display pilot… just like all the other pilots participating in the displays’. The DC advised that responsibility for ensuring the display instrument was being followed on the day of the event was with the Ringmaster.
The DC self-identified as the ‘air display liaison’ which was also reflected on the Airservices Australia letter of agreement (airspace arrangement) and the City of Perth Skyworks emergency contact list. Despite this, the DC had entered his name as DO on the 2015, 2016 and 2017 application forms.
With regard to the approval process, the DC reported that different CASA officers had different application requirements. He indicated his role was to provide information to CASA, to allow them to assess and approve the display. The DC said that CASA had requested to observe a certain routine in the past, before issuing the display approval. It was therefore the DC’s opinion that it was ultimately CASA’s decision as to whether or not to approve a pilot and their display.
In contrast, several CASA officers reported it was the DO/DC’s responsibility to ensure that a pilot and/or display was suitable, before including them in the application. However, CASA officers also stated that it was ultimately the individual pilot’s responsibility to satisfy themselves that they were capable of conducting the intended display.
The DC reported that he did not necessarily have the opportunity to know each pilot and their display, however he would not invite a pilot that he felt was not suitable to be part of the display. The DC noted that some years certain pilots and/or aircraft were not available but on the whole the applications were similar each year, with just an occasional display name change. Other than inviting the participation of the Mallard, the DC could not recall the last time a new display was introduced.
Ringmaster
The Ringmaster carried out a portion of the DC’s responsibilities as they related to controlling the flying program on the day.
The Ringmaster held a Commercial Pilot (Aeroplane) Licence and was a flight instructor. She reported having been involved in the event for about nine years, first as an observer with the DC in a Caravan, then assisting the previous Ringmaster during one display, before taking on that role. The Ringmaster described her role as coordination of the display aircraft and monitoring them for good separation. She advised she would sometimes offer or approve a request for additional fly-bys where time permitted. The Ringmaster also coordinated the various banner/flag aircraft between displays.
For the 2017 display, the Ringmaster was located in a room on the twelfth floor of a hotel, situated on the northern side of Langley Park that provided a full view of the display area (Figure 11). An assistant located with the Ringmaster provided support in visually monitoring aircraft movements when the Ringmaster was conducting radio communications. The assistant advised he was a flight instructor and had been in that role for the last four or five years.
When the approval for CQA’s third pass was granted by the Ringmaster, the assistant reported that their vantage point and the position of the sun made it difficult to identify exactly what the aircraft was doing over Melville Water (Figure 11) prior to returning to the display area. Although the Ringmaster did not specify the manner in which the Mallard was to return for the third pass, the assistant expected the approach to be via the standard procedure, behind the city, and was surprised when he realised CQA was re-entering Perth Water directly. He reported that CQA may have flown over boats[22] lower than the authorised height, but as the moment had passed, there was no gain in immediately contacting the pilot about it. The Ringmaster advised that she did not observe CQA until just prior to the accident as she was communicating with a banner‑towing helicopter via radio.
Figure 11: The view of Langley Park from the Ringmaster’s vantage point
Source: City of Perth
The Ringmaster had a copy of the Instrument, emergency contact list and display schedule with her on the day. The display schedule contained basic detail of the actual display routines, however it was reported they were generally similar each year. Further, she did not necessarily know who was on board each aircraft, other than the schedule‑listed pilot. The Ringmaster generally didn’t communicate with pilots during their display, so as not to distract them, but would make a call if there was something unsafe.
Suitability assessment for key roles
The CASA air display manual in effect at the time of the occurrence made limited reference to the suitability or experience required for individuals to hold key roles. The guidance was that the DO should have considerable aviation experience if also assuming the function of the DC, or otherwise appoint a suitably qualified person, preferably with display experience. There was no mechanism detailed for assessing the suitability of individuals for the roles and no additional training or accreditation.
By contrast, the Civil Aviation Authority United Kingdom (CAA UK) published Civil Aviation Publication (CAP) 403 Flying Display and Special Events: A Guide to Safety and Administrative Arrangements. CAP 403 provided detailed information about the roles and responsibilities of event organisers and participants. From 1 May 2017, the UK CAA implemented Flying Display Director (FDD)[23] accreditation. The accreditation scheme required the applicant to ‘demonstrate their knowledge, experience and capability against a number of FDD competencies’ including:
regulatory compliance
maintaining flying discipline
risk management
‘understanding of human factor influence on the safety of flying displays’.
The applicant was also required to undergo behavioural and attitudinal fitness assessments.
If successful, the FDD would be authorised to an appropriate tier level, based on degree of display complexity, for a period of three years and must maintain currency for re-accreditation. The United States and New Zealand had similar programs to ensure the knowledge and suitability of the person primarily responsible for coordinating the event.
The CAA UK also required formal evaluation of potential display pilots and their intended routine. This involved having an authorised Display Authorisation Evaluator (DAE) evaluate and mentor a pilot, at which point the pilot can apply for a Display Approval (DA), which was required to participate in a CAA UK authorised event.
Similar to the FDD, to be granted a DA a pilot was required to undergo behavioural and attitudinal assessment to determine their suitability for a flying display role. The pilot’s DA was aircraft type and routine-specific. These accreditation requirements were established in the mid-1980s, with additional restrictions and formalised training introduced after the 2015 Shoreham Air Show accident (see the section titled Related occurrences). As with the FDD role, currency and re‑evaluation was required for re‑validation of the DA. At the time of writing, the United States had a similar pilot evaluation program for aerobatic pilots.
Additional guidance was provided by the CAA UK publication, CAP 1047 Civil Air Displays – A guide for pilots. This publication was ‘intended to provide advice to display pilots to help them avoid the pitfalls which have been experienced in the past’. Topics included personal fitness, planning and practicing for displays, and what to do on display day.
CASA approval and oversight of air displays
Regulations and guidance material
Australia’s Civil Aviation Act 1988, through the Civil Aviation Regulations (CARs) and Civil Aviation Orders (CAOs), provides CASA with the authority to regulate exhibitions of flying, commonly referred to as air displays, flying displays or airshows involving civil aircraft.
CAR 156 and CAO 29.4 cover the regulatory requirements as they relate to air displays. CAR 156 relates to flying over public gatherings. CAO 29.4 outlines the application process and specifies the conditions of approval, planning and control requirements. The order states that an air display shall not be conducted without the written approval of CASA and that the organiser shall be responsible for ensuring that the applicable regulations are met.
CASA also developed the Air Display: Safety and Administrative Arrangements (air display manual) as guidance material to be read in conjunction with the regulations.
Air Display Manual
The air display manual provided guidance on the minimum safety and administrative procedures necessary to run an air display. It outlined the responsibilities of key personnel involved in an air display, including that of the DO, DC and display pilot (flight crew) (see the section titled Air display roles and responsibilities). The guidance in effect at the time of the display approval process was version 1.3 (November 2010). While the air display manual contained detail with respect to responsibilities of the DOs, it was limited in guidance with respect to assessing an application to an expected standard.
In comparison with other jurisdictions, the United States FAA order 8900.1 Volume 3, Chapter 6, Section 1 contained detailed guidance around processing and assessing applications for aviation events (including air displays) to determine whether to issue a certificate of waiver or authorisation to an applicant.
At the time of the occurrence, a revised air display manual had been drafted. Subsequently, version 2.0, significantly revised and renamed the Air Display Administration and Procedure Manual, was published in September 2017, with version 3.0 published in April 2018.
Receipt and processing of air display applications
Applications to conduct air displays were generally submitted to the local regional CASA office, using Form 696 Application for approval to conduct an airdisplay, along with supporting documentation. After assessment of the application, the officers provided advice in the form of a ‘reason for decision’ to the authorised CASA delegate. If approved, the delegate then issued an Instrument under CAO 29.4, identifying the person, or organisation, authorised to conduct the air display. This Instrument formed the approval and permission to conduct the air display, including any CASA‑imposed conditions.
As part of this investigation, the ATSB reviewed Skyworks display approvals conducted by the Western Region (Perth) office, as well as those for the Great Eastern Fly-In conducted by the sport aviation office between 2015‑2017.
Staff in both the Perth and sport aviation offices developed forms or checklists to assist the display approval process. The Perth office developed an ‘Air Display Energy Management’ form, which was used in the 2015‑2017 air display documentation to provide detail for some aerobatic and specialised displays. The form was titled ‘CASA Western Region – Air Display Form’ and had provision for ‘participant’ and ‘DC’ signatures. However, none of the ‘Energy Management’ forms reviewed had been endorsed by the DC.
The sport aviation office developed a spreadsheet to monitor air display pilots’ medicals, licence and endorsements, and aircraft registrations and airworthiness categories. This office also developed a risk assessment document for DOs to complete and submit with their application, and a checklist to monitor the progress and requirements of the approval process. It was reported these additional measures were implemented to ensure consistency and standardisation of the sport aviation office approval process.
The region-specific documents were not referenced in the air display manual nor disseminated more widely. Additionally, the Perth and sport aviation offices were also unaware of the documentation each other had developed.
Air display surveillance
The CASA Western region office increased their involvement in the 2017 air display in response to a drone sighting in Perth Water and a near-collision involving display aircraft, just outside Area Alpha, during the 2016 event.
The office initiated a surveillance activity, which included ramp checks [24] at Jandakot Airport before the air display, and observations of the City of Perth and Police coordination centre and Ringmaster locations. CASA advised the DC of these planned activities in early January 2017 and subsequently met to discuss the purpose of the activities and to address concerns of the DC that the surveillance activity may distract the involved pilots.
After CASA staff escalated the DC’s concern internally, the decision was made to continue with the planned surveillance activities as there had not been any formal surveillance of the event for a significant time period, and the staff understood that the upcoming version of the air display manual would require such activity in the future.[25]
CASA officers attended Jandakot Airport on 26 January 2017, from 1330 until about 1630. The surveillance included a series of ramp checks, observation of formation briefs and general liaison with participants. Due to the proximity of the ramp checks to the display, there was reported concern among the DC, Ringmaster and some of the air display pilots that the checks may have caused stress or distracted pilots immediately prior to flying.
It was reported to the ATSB that the pilot of CQA elected to depart from Serpentine Airfield (instead of Jandakot Airport) to avoid the surveillance activity. While that could not be verified, departure from Serpentine meant there was no opportunity for either CASA, the DC or the pilot of MOX to observe or engage with the pilot prior to the display.
While the Perth office reported they generally attended the pre-display briefings, they did not have a policy to observe, and did not routinely attend the air display. By contrast, the CASA sport aviation office regularly attended the air displays they approved. They reported that this allowed them to observe that the requirements of the display authorisation were being upheld and provided assurance that the documented Instrument was relevant. In addition, the sport aviation office reported that regular attendance of air displays fostered good cooperation with organisers and participants.
Air display risk management and governing framework
Defining risk management
International Standard ISO 31000:2018 Risk management – Guidelines defines risk as the ‘effect of uncertainty on objectives’. That is, deviation from the expected. Risk management is defined as ‘coordinated activities to direct and control and organization with regard to risk’. Some of the key risk management principles include that it:
be integrated into organisational (or in this case, event-based) activities
provide a structured and comprehensive approach, allowing consistent and comparable results
be dynamic, as risks can emerge or change as the context changes
use the best available information, so that both historical and current information from all stakeholders can inform the risks.
The risk management process in ISO 31000:2018 is outlined in Figure 12, and defined as involving:
…the systematic application of policies, procedures and practices to the activities of communicating and consulting, establishing the context and assessing, treating, monitoring, reviewing and reporting risk.
This process is designed to be an ‘integral part of management and decision making’ and can be applied at any level including operational matters.
Figure 12: The risk management process
Source: International Standard ISO 31000:2018 Risk Management - Guidelines
The elements of this risk management process relevant to air display preparation, included:
Communication and consultation: where relevant expertise is brought together to ensure the right information is considered when identifying, assessing and controlling risk. In this case, the input of stakeholders such as the City of Perth, DC, Ringmaster, CASA and the display pilots.
Scope: In the context of an air display, the scope should include all activities that may affect the safety of the flying operations.
Risk identification: the purpose of risk identification is to ‘find, recognise and describe risks that might help or prevent’ the desired outcome. In this context, it is important that regulators and DOs consider potential threats, indicators of emerging risks (for example, late inclusion of a new display), limitations of knowledge and time-related factors.
Risk treatment: the purpose is to ‘select and implement options for addressing risk’, including whether a certain risk is to be avoided, changed, shared or retained. Relying on individual pilots to manage their own risks when taking part in an air display is a limited treatment strategy, but combined with more systematic approaches and the collective knowledge of others allows for improved identification of defences.
There is further guidance about the risk management process in ISO 31000:2018 and the September 2017 CASA air display manual.
The concept of a risk framework
As outlined in ISO 31000:2018, a framework for managing risk is designed to ‘assist [organisations] in integrating risk management into significant activities and functions’ for good governance. ‘Framework development encompasses integrating, designing, implementing, evaluating and improving risk management’ across an organisation or group of people.
The United Kingdom (UK) Department for Transport commissioned a study in response to a recommendation from the UK Air Accident Investigation Branch investigation of the 2015 Shoreham accident (see the section titled Related occurrences). The resulting report, A Review of UK civil flying display and special event governance, discussed the concept of governance and how it can range from structured to informal in nature. A governance framework was described as providing ‘an organisation or a group of individuals with common objectives, and reflects the interrelated relationships, factors and other influences on them’. The report stated that good governance should:
provide a set of processes and procedures to deliver clear direction and oversight to industry
distil down specific roles, accountabilities and communications, and
provide a feedback loop that can identify trends and respond to changing circumstances, challenges and regulatory needs.
A visual representation of such a framework, based on good governance principles, was developed to review the UK civil aviation flying display activities, existing around the time of the Shoreham accident. It depicted interactions between the government, the CAA UK and industry (Figure 13). It defined the governance infrastructure as the ‘people, processes and systems to manage day to day activity and reporting’. The top half of the diagram shows those activities that the CAA UK have primary responsibility for defining, developing and participating in, including:
performance – including monitoring of safety performance indicators, and conducting audits
strategy – including reviewing and updating legislation
organisation – including defining the roles of those organising the air display, accrediting the display organisers and briefing display pilots
talent – including developing CAA UK staff skills, mentoring display pilots and shadowing display organisers
The bottom half outlined the areas to be delivered by industry, where the CAA’s responsibilities were more related to understanding, oversight and monitoring (rather than active involvement). This included the planning of the display, the operations themselves, and compliance with regulations.
Throughout this, the CAA UK is also responsible for establishing a risk management framework, including the application of a risk assessment process, auditing flying displays, and setting a risk matrix applicable for flying displays.
Figure 13: United Kingdom civil flying display governance framework
Source: Helios, 2018
Risk management for air displays
In April 2016, CASA convened a working group to update the air display manual. That group identified that the risk assessment process was likely an appropriate and effective tool for the assessment of air display approvals. Despite that, the air display manual in effect for the 2017 air display did not include a requirement to complete a risk assessment as part of the planning or approval processes. However, the September 2017 version of the Manual included a requirement for the DO to ‘compile and conduct [a] risk assessment’, and provided comprehensive guidance in an appendix.
As previously mentioned, the CASA sport aviation office advised that they expected DOs to include a risk assessment as part of their application. An example reviewed by the ATSB for the Great Eastern Fly-In included risks associated with a range of operational activities, including flight and group operations, maintenance, display pilot matters and airspace.
In reviewing other States’ requirements for their air displays, the ATSB noted that the Civil Aviation Authority of New Zealand (CAA NZ) included in their Advisory Circular AC‑91‑1 Aviation Events that the organiser was expected to risk assess the activity. They add that:
The responsibility of implementing and monitoring risk removal and risk mitigation steps falls to the organiser, flying display director and flying display committee. They should therefore all be involved in the risk assessment of the aviation event.
Similarly, the CAA UK CAP403 Flying Display and Special Events: Safety and Administrative Requirements and Guidance outlined that ‘risk assessment is an essential element in the production of any safety plan…Flying Display applicants are required to submit information about any risks that will be actively managed during the event to CAA as part of the display application process’.
Skyworks risk management activities
The City of Perth developed a risk management plan, covering activities associated with the events and coordination around Skyworks, including the air display. It outlined key responsibilities for stakeholders and the tools that were used to identify, assess and control risk. One of these tools was a risk register, which included a number of aviation-related risks such as ‘aircraft/skydive incident causing injury or ill health’. The mitigation for that risk included the provision of the air display approval, and proposed surveillance, from CASA, a landing area exclusion zone and an emergency response plan. The DC provided input into this risk management plan or risk register. Risks identified from previous years’ events included the effects of falling debris, an ‘aircraft incident on Perth Water’, particularly among the moored boats, and skydivers landing in unintended areas.
A near‑collision occurred during the 2016 air display involving a banner tow aircraft and a group of display aircraft, just outside of Area ALPHA. The occurrence prompted the DC, in late January 2016, to request that CASA assist with a modification to area ALPHA for the 2017 display, to reduce the risk of a repeat occurrence. In conjunction with Airservices Australia, CASA’s Office of Airspace Regulation requested that the DC complete a risk assessment, relating to the proposed airspace changes for the 2017 display. The DC questioned the need for the risk assessment when it had not been required previously. In addition, the DC advised CASA he would sign a risk assessment that CASA prepared, when he returned from an overseas trip in November 2016. In response, CASA encouraged him to develop it as a ‘living document’ rather than rely on his experience in the conduct of the air display and examples of risks were provided to the DC. A completed risk assessment (limited to the scope of airspace changes) was ultimately supplied to CASA and the airspace changes were authorised.
In the lead-up to the air display, the CASA Perth office liaised with the DC on some concerns such as the draught of the Mallard in the water and the single‑engine performance. However, apart from the requested risk assessment relating to airspace matters, there was no formal or systematic way that other types of operational risks were identified, assessed and controlled. There was also no requirement to do so under the current regulations.
Related occurrences
Within limitations of the ATSB occurrence database, there were approximately 22 air display‑related occurrences in the ATSB database between 1969 and 2017. Thirteen of those occurrences resulted in a fatality, therefore averaging one fatal accident every 3.7 years. The majority of the occurrences were related to aircraft handling, resulting in loss of control and collision with terrain.
The ATSB also reviewed other states’ investigations into air display accidents, particularly those involving passengers and/or spectators. The scope of the review was to gain appreciation of risk factors to spectators, and where lessons learned had resulted in improvements to the planning and approval of air displays. A number of occurrences were identified and two of these are discussed below.
United Kingdom
The Air Accidents Investigation Branch, United Kingdom investigated the accident involving Hawker Hunter T7, registration G-BXFI near Shoreham Airport on 22 August 2015. The aircraft crashed on to the Shoreham Bypass while performing at the Shoreham Airshow, fatally injuring 11 road users and bystanders. A further 13 people, including the pilot, sustained other injuries.
Beyond examining the actions of the pilot, the investigation found that:
…the parties involved in the planning, conduct and regulatory oversight of the air display did not have formal safety management systems in place to identify and manage the hazards and risks. There was a lack of clarity about who owned which risk and who was responsible for the safety of the air display, the aircraft, and the public outside the display site who were not under the control of the show organisers.
The regulator believed the organisers of air displays owned the risk. Conversely, the organiser believed that the regulator would not have issued an approval for the display if it had not been satisfied with the safety of the event…and the display organiser believed that it was the responsibility of the operator or the pilot to fly the aircraft's display in a manner appropriate to the constraints of the display site.
No organisation or individual considered all the hazards associated with the aircraft’s display, what could go wrong, who might be affected and what could be done to mitigate the risks to a level that was both tolerable and as low as reasonably practicable.
Controls intended to protect the public from the hazards of displaying aircraft were ineffective.
Additional detail in the report included consideration of risk to spectators outside the event, non‑participants (general public in the area) and proximity of residential, industrial and recreational areas, including schools and hospitals.
United States
On 16 September 2011, an experimental single-seat North American P-51D collided with terrain while participating the National Championship Air Races in Reno, Nevada. The pilot and 10 people on the ground sustained fatal injuries and at least 64 others were injured. The National Transportation Safety Board (NTSB) investigation identified the aircraft was conducting a turn just prior to the loss of control. The NTSB made several recommendations, including evaluation of the course design and safety areas to minimise manoeuvring near, and potential conflicts with, spectators. The event organiser subsequently relocated the course and primary spectator area to ‘create and maintain a greater distance’ between the racers and spectators.
Following two low fly-bys along the Langley Park foreshore as part of the City of Perth Australia Day Skyworks event, the pilot of Mallard VH‑CQA (CQA) manoeuvred his aircraft in order to conduct a third pass. During the final positioning turn, CQA rolled left, pitched nose‑down and collided with water. The pilot and passenger were fatally injured, and the aircraft was destroyed. This analysis will examine the:
loss of control
pilot’s actions in returning to the display area for a third pass
carriage of a passenger
regulatory framework for approval and oversight of air displays.
As part of the analysis, comparisons have been drawn with other country’s regulations, guidance and practices as a means of benchmarking other methods for managing air displays. Other countries have also published extensive guidance material and some have dedicated air display organisations to support those organising and participating in air displays.
Loss of control
Analysis of recorded flight and video data, and witness reports identified that the aircraft stalled in the positioning turn for the third pass. Such a loss of control in this aircraft type at the relatively low operating altitude meant the situation was unrecoverable before contact with the shallow water.
Technical examination of the aircraft did not identify anything that contributed to the accident. In the absence of a problem with the aircraft, the stall most likely resulted from a handling error and there were several factors that increased the risk of that occurring.
The pilot had limited recent experience operating the Mallard and had not previously participated in a display involving low-level turns within a confined area. Considering this, and noting the limited opportunity available due to his late inclusion and licencing issue, the pilot had not practiced for the event.
The pilot’s lack of familiarity was intended to be mitigated by following another participating aircraft, VH‑MOX (MOX), during the display sequence and having a pilot familiar with the display present in CQA. These defences were not effective however, as CQA parted company from MOX prior to returning to the display area in a different manner to that associated with the first two passes and there was no accompanying pilot on board CQA during the flight.
Additionally, although current and recent in accordance with the regulations, the pilot had not undergone any formal training in the Mallard in the five years since his endorsement and had satisfied the intervening biennial flight review requirement in a different aircraft type. This was despite the Mallard being a type-rated aircraft, considered as having performance or handling techniques that warranted specific training and flight reviews. The lack of assessment in the Mallard since endorsement was a missed opportunity to objectively confirm the pilot’s competency, or identify and correct any degraded skills specific to operation of that aircraft.
Finally, although not a requirement, the aircraft was not fitted with a stall warning device that may have alerted the pilot to the developing situation in sufficient time to take corrective action.
There was insufficient evidence to establish the extent to which any of these factors influenced the development of the accident. Similarly, the degree to which a focus on participating in the event may have distracted the pilot from operating the aircraft could not be determined.
Returning for the third pass
The pilot of MOX only conducted the two planned passes and was unaware of the intention for a third by CQA until it was requested of the Ringmaster. This impromptu action was contrary to the briefed plan that the two aircraft would fly in company to mitigate against potential issues with the pilot of CQA’s unfamiliarity with the display.
After completing the second display pass, MOX departed the display area bound for a return to Jandakot Airport, followed by CQA. By the time CQA turned to return for the third pass, it was well inside Melville Water. On approving the third pass, the Ringmaster did not offer any direction regarding its conduct and the pilot elected to track directly back to Perth Water. The return to the display area was conducted at low altitude over the built-up area of The Narrows and moored watercraft, which was a deviation from the display approval.
Although not observed by the Ringmaster, the assistant assessed that CQA may have passed over boats below the authorised height during the return for a third pass. However, because CQA had then effectively joined the downwind leg of the accepted orbits over Perth Water, no immediate action was considered necessary.
Left orbits in the Mallard within the confines of Perth water were possible while adhering to the display conditions. However, the requirement to remain clear of the spectators, including watercraft, meant that the area was relatively confined. As a result, manoeuvring within the display area, as opposed to entering it in the prescribed manner around the city, required turns at higher bank angles and lower altitudes, which reduced the margin for error. Had CQA re-entered the display area using the standard procedure, the manoeuvres required to position for the pass would have been relatively benign and significantly reduced the risk of mishandling the aircraft.
Pilot decision making
Nature of decision-based errors and motivational factors
In considering whether the pilot’s actions in returning for the third pass were reasonable to him at the time, it is useful to consider the nature of decision-based human error. One such example, knowledge-based mistakes, are defined as ‘errors brought about by a faulty plan or intention’. They arise in novel situations with ‘resource limitation (bounded rationality) and incomplete or incorrect knowledge’ (Reason, 1990) and likely arise from a lack of appreciation of potential consequences (Harris, 2011). Knowledge-based mistakes can be significantly influenced by certain ‘performance shaping factors’ (O’Hare, 2006). These can be external factors, such as environmental conditions, equipment design and procedures, or internal factors, such as a pilots’ emotional state, physical condition, stress, experience, and task knowledge.
As discussed, the pilot was not well-prepared for the planned display. Additionally, although the pilot attended the pre-display briefing and had access to the display procedures, CQA had likely only ever planned to follow MOX and therefore it is possible that the pilot placed less emphasis on familiarisation with the complete display conditions and procedures. These factors may have contributed to a level of unfamiliarity with the task that resulted in the pilot flying the display with an incomplete or incorrect knowledge and/or appreciation of the potential consequences.
As part of the investigation, the ATSB also considered the motivational effects of being part of event such as an air display. The pilot was reportedly enthusiastic about being involved and was known to enjoy displaying what was a unique and interesting aircraft. While it is difficult to quantify the effect of the pilot’s emotional state in this occurrence, these elements have the potential to influence pilot behaviours, which is reflected by the inclusion of display pilot attitudinal assessments in other jurisdictions.
Handling human factors considerations in air displays: other countries
The human factors considerations of air displays is a topic that has gained more traction in recent years. As part of the Civil Aviation Authority United Kingdom (CAA UK) response to the Shoreham accident findings (one of which required them to undertake a study of error paths that lead to flying display accidents), a workshop called Human Factors in Flying Displays was held in 2017, and attended by about 35 DOs and pilots. One of the topics of discussion was the ‘personal qualities and characteristics of display pilots’ and the DOs. Boundaries between ‘confidence and arrogance’ were discussed, and the importance of promoting learnings and good practices among display pilots.
Additionally, the CAA UK-commissioned study authored by Butler and others (2018) raised some considerations for the future, finding that:
the processes related to the assurance of the competence of air display pilots was a recurring contributory factor highlighted in accident reports. These included training, supervision, practical experience and assessment.
They included a recommendation in their report for display pilots to undertake human factors training, provided by the CAA UK to ‘ensure there is an exchange of expertise across the display community’.
Other States have recognised the need to improve air display pilots’ overall proficiency. For example, the Federal Aviation Administration (FAA), United States, established the Aerobatic Competency Evaluation (ACE) program where pilots must obtain a Statement of Aerobatic Competency (SAC) card prior to conducting aerobatics, or other defined manoeuvres. The FAA delegated the ACE program to the International Council of Air Shows (ICAS), subject matter experts.[26] ICAS published the Air Show Performers Safety Manual to ‘help establish an understanding of the risk factors attendant to air show performances’.
Summary
While the precise reasons for the pilot’s actions will remain unknown, there were several factors that may have influenced the pilot’s decision making, and which reinforce the importance of planning and practicing for displays. A safety message was highlighted in the CAA UK’s guide for display pilots, which emphasised:
Never be tempted to make unrehearsed changes to your display routine and do not undertake any manoeuvres you have not practiced….Stick to your planned routine but always be prepared, particularly at hot and high displays, for reduced aircraft performance…Never press on into a manoeuvre with less than ideal start conditions.
Carriage of a passenger during the display
Participation in an air display is a specialised aviation activity that frequently involves flying the aircraft in a non‑standard manner and in unique locations. As such, there is an increased risk associated with this type of flying and for this reason passengers are not permitted to take part.
This requirement was clearly stated in the conditions of the display. The pilot had also received the display briefing the night before, reinforcing this condition. Additionally, the pilot had previously been informed by staff from the Civil Aviation Safety Authority (CASA) that the person carried was a passenger and was not considered as crew for the purpose of an air display. Despite this, he carried this passenger during the Perth display, which increased the severity of the accident outcome.
Regulatory framework for approval and oversight
According to the International Standards ISO 31000:2018 Risk management – Guidelines and a review of the UK CAA’s approach towards air displays, good governance in this context comes from activities such as:
having processes and procedures for the industry and the regulator to work by
clearly delineating and providing guidance in the roles and responsibilities of organisers and pilots
monitoring safety performance of those involved in the planning and preparation of the air display including ensuring that regulator staff are adequately prepared.
The regulator’s responsibilities are met by ensuring there are the right ‘people, processes and systems to manage day to day [air display] activities and reporting’ (Helios, 2018).
With respect to air displays in Australia, although certain regulatory processes did exist, CASA did not have an effective framework to consistently approve and oversight air displays. This was predominantly due to the following factors, which increased the likelihood that key safety risks associated with the conduct of the air display would not be adequately managed. It could not be determined whether the regulatory framework in place at the time of the accident contributed to it.
Air display approval guidance
The CASA‑published manual, Air Displays: Safety and Administrative Arrangements (air display manual) to provide ‘guidance on the minimum safety and administrative procedures necessary to run such an event’. However, there was no comprehensive guidance for the assessment of an air display application or oversight of the event, including the expected standard for certain criteria.
While those assessing the applications had shared their methodology and local knowledge within their office, this information was not readily accessible to all offices. As regional offices sought to independently ensure completeness and standardisation of their assessment processes, they developed local procedures, forms and checklists. Variability in assessment and approval practices increases the likelihood of applying an inconsistent process or standard to the task, increasing the risk that key safety aspects may be overlooked.
In contrast, both the FAA and CAA UK published documents that provided their staff with specific guidance and processes for assessing and approving an air display, which in turn provides some assurance of standardisation.
Roles and responsibilities
Air displays require careful management and coordination. The scale and complexity may differ, but any lack of clarity around key roles will affect how well they are managed. The roles of the display organiser (DO) and display coordinator (DC) are vital to the planning and safe operation of each air display. For this display, the roles were not clearly or consistently defined and there were differences in the understanding of who held those roles, exactly what their responsibilities were or the standard those responsibilities were expected to be carried out. This meant that key, safety‑related elements of the air display planning and oversight were more likely to be overlooked.
These points indicated that CASA’s processes were not effective in ensuring that key personnel were fully aware of their responsibilities or that they were suitably equipped to carry them out to the expected standard. By comparison, the CAA UK, FAA and CAA NZ have all established accreditation programs for persons taking on the role of the DO or DC (or equivalent roles). While the accreditation process varies between countries, the concept is similar. In addition to requiring knowledge of the regulations and role responsibilities, the candidates are individually assessed for suitability including behavioural and attitudinal fitness for the role. Essentially, the accreditation program is designed to provide organisers, and in some cases participants, with the knowledge and skills to effectively and safely plan and coordinate and/or participate in an air display. As such, it provides necessary assurance to regulators that the roles will be carried out with consistency and to the expected standard.
Identification and treatment of risk
The risk management process is designed to be an ‘integral part of management and decision making’ (ISO, 2018) for an event such as an air display. If organisers and regulators take the opportunity to systematically identify, assess and treat risks, it is possible to reduce the impact of hazards on the safety of the event. The application of the risk management process will not, in all likelihood, capture every possible risk, but the process can trigger identification and validation of those that are foreseeable, and prioritise their treatment. In particular, it increases the chances that changes, such as the late inclusion of an unfamiliar pilot in the air display, can be considered in terms of the potential introduced risk.
The air display manual current at the time of the accident was the main reference for organisers however, it did not include a requirement for any risk management activities to be done. It was therefore less likely that CASA staff (unless requiring a risk assessment as part of their local procedures) involved in the approval and oversight of air displays were in a position to review organisers’ perceptions of operational risks, or apply systematic methods of risk management.
In this case, CASA identified a number of safety-related risks, such as the pilot not having the appropriate endorsement on the Mallard and the benefit in having the DC on board CQA to mitigate against the pilot’s inexperience. However, these were not identified through any systematic means, and the treatment measures were sometimes not implemented (for example, the DC was not on board CQA for the display), or had other unintended consequences (authorising the pilot’s participation two days out from the display significantly limited his available time to prepare and practice). These examples, plus the absence of any documented processes or any requirements for the staff organising air displays to use systematic risk management methods, reduced the chances that identified risks were going to be treated adequately and controls implemented.
It is noted that CASA has revised the air display manual since this accident to include a requirement for a formal risk assessment to be completed by DOs, which reflects the best-practice approach to identifying and controlling display risks (see the section titled Safety issues and actions). However, using a risk-based approach for the assessment and approval process itself would probably provide additional safety benefit.
From the evidence available, the following findings are made regarding the loss of control and collision with water involving the G-73 Mallard aircraft, registered VH-CQA 10 km west‑south‑west of Perth Airport, Western Australia on 26 January 2017. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
The pilot returned the aircraft to the display area for a third pass in a manner contrary to the approved inbound procedure and which required the use of increased manoeuvring within a confined area to establish the aircraft on the display path.
During the final positioning turn for the third pass, the aircraft aerodynamically stalled at an unrecoverable height.
The pilot's decision to carry a passenger on a flight during the air display was contrary to the Instrument of Approval issued by the Civil Aviation Safety Authority for this air display and increased the severity of the accident consequence.
Other factors that increased risk
The Civil Aviation Safety Authority (CASA) did not have an effective framework to approve and oversight air displays, predominantly due to the following factors:
While the Air Display Manual provided guidance to organisers conducting an air display, it did not inherently provide the processes and tools needed for CASA to approve and oversee one and no other documented guidance existed.
Unlike the accreditation models adopted by some other countries, CASA did not have a systematic approach for assessing the suitability of those responsible for organising, coordinating and participating in air displays.
CASA did not have a structured process to ensure that risks were both identified and adequately treated.
The combination of these factors significantly increased the likelihood that safety risks associated with the conduct of the air display were not adequately managed. [Safety issue]
Safety issues and actions
The safety issue identified during this investigation is listed in the Findings and Safety issues and actions sections of this report. The ATSB expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
Depending on the level of risk of the safety issue, the extent of corrective action taken by the relevant organisation, or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue safety recommendations or safety advisory notices as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: The Civil Aviation Safety Authority (CASA) did not have an effective framework to approve and oversight air displays, predominantly due to the following factors:
While the Air Display Manual provided guidance to organisers conducting an air display, it did not inherently provide the processes and tools needed for CASA to approve and oversee one and no other documented guidance existed.
Unlike the accreditation models adopted by some other countries, CASA did not have a systematic approach for assessing the suitability of those responsible for organising, coordinating and participating in air displays.
CASA did not have a structured process to ensure that risks were both identified and adequately treated.
The combination of these factors significantly increased the likelihood that safety risks associated with the conduct of the air display were not adequately managed.
Safety recommendation description: The Australian Transport Safety Bureau recommends that the Civil Aviation Safety Authority undertake further work to enhance their tools and guidance for air display approval and oversight, and procedures to ensure the suitability of those responsible for organising, coordinating and participating in air displays.
Sources and submissions
The sources of information during the investigation included the:
Civil Aviation Safety Authority
Air Accidents Investigation Branch and Civil Aviation Authority, United Kingdom
National Transport Safety Board and Federal Aviation Administration, United States
National Transport Safety Committee, Indonesia
Civil Aviation Authority, New Zealand
International Council of Airshows
Perth Air Display organisers, participants and witnesses
City of Perth
G-73 and other float plane pilots
Bureau of Meteorology
Airservices Australia.
References
AAIB, Aircraft Accident Report AAR 1/2017 – G-BXFI, 22 August 2015, Air Accidents Investigation Branch United Kingdom
ATSB 2009, Avoidable Accidents No.1 Low-level flying, Australian Transport Safety Bureau, Aviation Research and Analysis publication AR-2009-041
Boud and McFarlane, 2018 Review of UK civil flying display and special event governance, Hampshire, United Kingdom
Butler and others, 2018, Human Factors in Air Displays: Transfer of Behaviours and Error Path Study, Health and Safety Laboratory.
CAA UK, Civil Aviation Publication (CAP) 403 Flying Display and Special Events: A Guide to Safety and Administrative Arrangements, Civil Aviation Authority United Kingdom
CAA UK, Civil Aviation Publication (CAP) 1047 Civil Air Displays – A guide for pilots, Civil Aviation Authority United Kingdom
CASA 2017, Air display administration and procedure manual, Civil Aviation Safety Authority
Harris, 2011, Human Performance on the Flight Deck, Ashgage Publishing Ltd, London, United Kingdom
International Standard ISO 31000:2018 Risk management – guidelines, ISO copyright office, Geneva Switzerland.
NTSB, Accident Brief AAB-12/01, Pilot/Race, The Galloping Ghost North American P-51D, N79111, Reno, Nevada, September 16, 2011, National Transport Safety Board
O’Hare, 2006, Cognitive Functions and Performance Shaping Factors in Aviation Accidents and Incidents, The International Journal of Aviation Psychology, pp.145-156
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the Civil Aviation Safety Authority, the City of Perth, the display coordinator, the ringmaster, the ringmaster’s assistant, the pilot of VH-MOX, the National Transportation Safety Board, the Federal Aviation Administration, the International Council of Airshows, the Civil Aviation Authority United Kingdom and the Air Accidents Investigation Board.
Submissions were received from Civil Aviation Safety Authority, the City of Perth, the display coordinator, the ringmaster, and the pilot of VH-MOX. The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Preliminary report
Report release date: 22/09/2017
What happened
On 26 January 2017, the pilot of a Grumman American Aviation Corp G-73 amphibian aircraft, registered VH‑CQA (CQA), was participating in an air display as part of the City of Perth Australia Day Skyworks event. On board were the pilot and a passenger. The weather was fine with a recorded wind of about 20 km/hr from the south-west and a temperature of about 39 °C.
The pilot of CQA was flying ‘in company’ with a Cessna Caravan amphibian and conducted a series of circuits that included low-level fly-pasts of the Langley Park foreshore (Figure 1). After the second fly-past, the pilot of CQA commenced a third circuit, while the Caravan departed the area.
Figure 1: CQA air display flight track, showing the first fly-past in yellow, the second in magenta and the third in red
Source: OzRunways Pty. Ltd., modified by the ATSB
As part of the third circuit, the pilot of CQA flew in an easterly direction, parallel with the South Perth foreshore, before commencing a left turn. This would have facilitated a third pass in a westerly direction along the Langley Park foreshore. During the left turn, CQA rolled left and pitched nose down, consistent with an aerodynamic stall[1] (Figure 2). The aircraft collided with the water and broke up. The pilot and passenger were fatally injured.
Figure 2: CQA just prior to the collision with water (looking north)
Source: Mike Graham
The ATSB completed the on-site phase of its investigation on 4 February 2017. No pre-existing aircraft defects, which may have contributed to the collision with water, were identified. The ATSB has retained several items and components from the aircraft for further examination. This includes a fuel totaliser, a navigation unit and a mobile phone.
The investigation is continuing and will include:
examination of numerous witness reports and images and a significant quantity of video footage taken on the day by members of the public, media outlets and so on
review of the aircraft’s maintenance records, operational records for recent flights and pilot training records
review of the meteorological conditions at the time
an examination of aircraft performance and other operational factors
further examination of the recorded flight radar, radio and Global Positioning System data
review of the planning, approval and oversight of the air display, including a focus on safety and risk management practices.
Should any critical safety issues emerge during the course of the investigation, the ATSB will immediately bring those issues to the attention of the relevant authorities or organisations. This will allow those authorities and organisations to consider safety action to address the safety issues. Details of such safety issues and any safety action in response will be published on the ATSB website.
The information contained in this web update is released in accordance with section 25 of the Transport Safety Investigation Act 2003 and is derived from the initial investigation of the occurrence. Readers are cautioned that new evidence will become available as the investigation progresses that will enhance the ATSB's understanding of the accident as outlined in this web update. As such, no analysis or findings are included in this update.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 21 January 2017, at about 0710 Eastern Standard Time (EST), the pilot of an Air Tractor AT‑401B aircraft, registered VH-DDW, was conducting aerial spraying operations at a property about 10 km NW of Mareeba Airport, Queensland. The pilot was the only person on board the aircraft.
Part way through spraying the load of chemical on an avocado plantation, the pilot climbed the aircraft at the end of a spray run, to about 200 ft above ground level. As the aircraft climbed, the engine suddenly made loud banging noises and the pilot estimated that the engine power reduced by about half.
Figure 1: Location of engine failure and accident site
Source: Google earth annotated by ATSB
The pilot levelled the aircraft and checked the fuel mixture and throttle controls but the engine did not respond. The power available continued to decrease as the pilot looked ahead for a suitable field to conduct a forced landing. The pilot selected a cleared area, but as the aircraft lost height, they realised that the aircraft was not going to make it to that field.
The pilot then radioed their loader driver[1] and advised that they had engine trouble, the aircraft was ‘going down’, and asked them to contact emergency services. The loader driver had heard the abnormal noise the aircraft’s engine was making, and responded immediately to the pilot.
As the aircraft descended, the pilot sighted powerlines ahead and assessed that the aircraft would probably not make it over them. Therefore, the pilot descended to pass under the powerlines. The pilot again spoke to the loader driver briefly on the radio. The aircraft then collided with several lychee trees and a vehicle that was parked in an orchard. The aircraft came to rest upright and was substantially damaged. The pilot sustained a minor injury.
Figure 2: Damage to VH-DDW
Source: Pilot
Operator report
The operator conducted an investigation into the accident and found the following:
The pilot had conducted a daily inspection, including an inspection of all engine cylinders, and found no signs of cracks. The aircraft had operated normally during the first two flights that day.
The aircraft was fitted with a Pratt and Whitney R-1340 radial engine that had 10,491 total hours and 478.1 hours since overhaul. The engine was inspected after the accident by a representative from an aircraft maintenance organisation and they determined that the number seven cylinder had failed (Figure 3). A crack was located around the circumference of the cylinder head, between the two spark plug holes. A recurring inspection of this area (CASA airworthiness directive AD/PW-P/19) was conducted about 91.9 hours prior to the accident at the periodic (100 hourly or 12-month) maintenance inspections.
Figure 3: Engine cracked number seven cylinder
Source: Aircraft operator, modified by the ATSB
Safety analysis
Post-accident inspection
A post-accident inspection revealed a cracked cylinder.
Pre-flight inspection
The aircraft had operated for about 91.9 hours since the periodic (100 hourly or 12-month) maintenance inspections.
The pilot conducted a pre-flight inspection at about 0500 and everything was normal, the oil was full. The aircraft was fitted with a chip detector,[2] which did not activate at any time. The engine indications indicated normal temperature and pressure immediately prior to the failure.
Weather and performance
The aircraft took off from Mareeba Airport, which is at an elevation of about 1,560 ft above mean sea level (AMSL), and was operating over a property at about 1,900 ft AMSL. The temperature was about 24 °C and there was 79% humidity. The conditions on the day may have reduced the aircraft’s performance. The pilot had substantial experience operating that aircraft in the local area.
The wind was a light westerly at about 2 kt and when the engine lost power the aircraft was tracking to the east, therefore with a light tailwind. This probably did not significantly affect the glide distance or the landing speed of the aircraft.
Forced landing sites
The area has orchards, houses and powerlines in most of the paddocks with uneven ground and creeks running through it, therefore there were limited sites suitable to conduct a forced landing. The pilot assessed that there was also no suitable road within gliding distance. The accident site was about 2.5 km from where the engine failed.
Chemical load
About 750 L of chemical was still on board the aircraft when the engine lost power. The pilot did not dump the load. The pilot commented that it was an oversight rather than a conscious decision not to dump the load. However, they further commented that they were trained to dump the load in the event of engine failure, and would do that in future if faced with a similar situation.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The number seven cylinder cracked, resulting in a loss of power.
The aircraft was operating at low level (below 200 ft AGL) in an area where there were limited options available to conduct a forced landing.
Safety message
In this accident, the time available to manage the engine failure meant that there were few options in regards to the selection of a landing area. The accident highlights the importance of taking positive action and maintaining aircraft control when conducting a forced landing, while being aware of flare energy and aircraft stall speeds.
The Aerial Agricultural Association of Australia advised that there is nearly always an uncertainty about whether to dump the load and they suggest that the only safe rule is ‘if in doubt, dump’. In a high stress situation such as an engine failure where there is limited time, it is important to apply appropriate emergency procedures. To mitigate against the effect of stress compromising memory even in a minor emergency, pilots should have embedded motor programs to handle emergencies in reactive mode.
The pilot was wearing a helmet and commented that although they were ‘flung’ from side to side during the accident sequence, the seatbelt held them firmly in place.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 21 January 2017, the crew of an Airbus A320 aircraft, registered VH-VNC (VNC), prepared to conduct Tigerair flight 491 (TT491) from Cairns to Brisbane, Queensland. The flight crew consisted of a training captain and a first officer under supervision. The first officer was in the role of pilot flying for the sector and the captain was pilot monitoring.[1]
The flight crew conducted a take-off and departure briefing based on the environmental conditions and runway in use, expecting to commence the take-off roll from the B5 taxiway intersection (Figure 1). They entered the take-off data into the iPad application and loaded the data into the flight management guidance computer.
At about 1511 Eastern Standard Time (EST), the surface movement controller (SMC) cleared the flight crew of a de Havilland DHC-8 (DHC-8) aircraft that had been parked on an adjacent bay to VNC, to taxi using taxiway C3 (and B) to holding point B4. About 30 seconds later, the SMC cleared the flight crew of VNC to taxi using taxiway C3 (onto taxiway B) to holding point B5, which was the clearance they had expected. The crew had briefed each other on that taxi route.
Figure 1: Cairns Airport diagram extract
Source: Airservices Australia – annotated by ATSB
VNC then taxied behind the DHC-8 along taxiway B. As the DHC-8 turned onto the runway at B4, the first officer of VNC inadvertently also taxied to holding point B4. After completing the ‘above the line’ pre-take-off checks (see Pre-take-off checks), at about 1515, the captain of VNC advised the aerodrome controller (ADC) that they were ready for take-off. The ADC cleared VNC to line up on the runway and, as the first officer taxied the aircraft onto the runway, the flight crew completed the ‘below the line’ pre-take-off checks.
About 1 minute later, the ADC cleared VNC for take-off. Immediately after the captain read back the take-off clearance, the ADC advised the crew that they were lined up at the B4 (not B5) intersection. The crew did not respond, so the ADC cancelled the take-off clearance and instructed them to hold position. The captain then confirmed that they needed to commence the take-off from B5. The ADC cleared them to turn around on the runway, exit using B4 and taxi to B5. The aircraft subsequently took off from the B5 intersection and the flight continued without incident.
There was a 403 m difference in available runway length, between the B4 and B5 taxiway intersections.
Pre-take-off checks
The pre-take-off checklist consisted of two parts: ‘above the line’ and ‘below the line’. The crew complete the first part (above the line) before reporting ready for take-off, and the second part (below the line) after the aircraft enters the runway.
Tower comment
The captain contacted the Tower controller after the flight to thank the controller for intervening and was advised that there had been a similar incident the previous day. The ATSB could find no record of any similar occurrences at Cairns Airport.
Safety analysis
Following the DHC-8
As the DHC-8 taxied immediately ahead of VNC, the flight crew may have been distracted by following the DHC-8 to B4. Although VNC had pushed back first, the DHC-8 flight crew had received their taxi clearance and commenced taxiing before VNC. There was no specific instruction to the flight crew of VNC to follow the DHC-8.
Cabin readiness
As the first officer turned the aircraft onto taxiway B4, the captain’s attention was on communicating with the cabin crew and observing their positions on the cabin video.
One of the items on the pre-take-off checklist (above the line) is ‘cabin ready’. The captain, as pilot monitoring, temporarily handed over responsibility for ATC communications to the first officer (as pilot flying), while they confirmed the status of the cabin. Because the captain had not heard the initial indication that the cabin was ready, they looked at the cabin video to check the cabin crew were seated and called the cabin crew on the interphone, who confirmed that the cabin was secure for take-off.
The captain then took back responsibility for ATC communications and returned their focus to cockpit activities. As the captain was busy liaising with the cabin crew as the aircraft turned onto B4, the likelihood that they would notice that the aircraft was approaching the runway on the incorrect taxiway was reduced.
Training flight
The first officer had completed 11 sectors and was under the supervision of the training captain. The first officer assessed their workload at the time as moderate. This was the first officer’s second flight into Cairns since joining the operator. The captain also commented that runway 33 was not the usual runway in use at Cairns (due to the prevailing winds). A lack of familiarity with the runway may have reduced the flight crew’s ability to detect the incorrect runway position when the aircraft was lined up on the runway.
The captain commented that the first officer was taxiing slightly faster than optimal coming up to the holding point. The captain may have been focused on monitoring the progress of the aircraft to ensure the aircraft stopped before the holding line, which may have distracted them from noticing the B4 taxiway sign (to the left of the taxiway).
Normally, the pilot flying would have completed the flight controls check earlier in the taxi and well before the holding point, but the first officer completed checking the controls as the aircraft approached the turn onto B4. The captain commented that the checks were all completed correctly and in the correct order, but slightly later than normal due to the relative inexperience of the pilot flying.
Pre-take-off checklist
The relevant ‘below the line’ check to confirm that the aircraft was prepared to take-off on the correct runway, was for the pilot flying to state ‘runway 33 confirm’, then the pilot monitoring to respond ‘runway 33 confirm’. While this checklist item provided confirmation of the runway, reference to an intersection was not part of the verbal check/response.
The first officer commented that confirming the intersection as well as the runway during the pre-take-off checks may prevent a similar incident occurring.
Potential overrun
The aircraft operator reviewed the ramifications of a departure from the B4 intersection with B5 performance take-off data. Initial calculations showed that in the event of a rejected take-off, either with all engines operating or one engine inoperative, would have resulted in a runway overrun.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The first officer taxied the aircraft to the runway holding point B4 instead of B5 and may have been distracted by following the DHC-8, which taxied immediately ahead of them and took off from the runway intersection with taxiway B4.
The captain was communicating with cabin crew and looking at the cabin video as the aircraft turned onto taxiway B4, which probably distracted them from verifying that they had turned into the correct taxiway.
Neither member of the flight crew recalled seeing the B4 holding point sign (to the left of the aircraft) at any time.
The first officer was under training and had only been to Cairns once previously, and runway 33 was not the usual runway in use. Lack of familiarity with runway 33 may have reduced the flight crew’s ability to detect the incorrect runway position when the aircraft was lined up on the runway.
The air traffic controller saw the aircraft at the incorrect intersection after clearing it for take-off and alerted the crew.
There was potential for a runway overrun in a rejected take-off situation if the aircraft had commenced the take-off run from the B4 intersection.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following safety action in response to this occurrence.
Aircraft operator
As a result of this occurrence, Tigerair has advised the ATSB that they are taking the following safety actions:
Safety awareness
Tigerair has distributed a Flight Training Notice to alert training and checking crew on both the A320 and B737 fleets to the event. Tigerair Safety will be publishing the event in their next Safety Spotlight newsletter.
Safety message
This incident highlights the importance of confirming that an aircraft is lined up for take-off at the correct intersection, or position on the runway, as well as the correct runway. Confirmation of runway heading is done by checking the aircraft’s magnetic heading with the runway direction once the aircraft is lined up on the runway. The intersection should be checked before the aircraft enters the runway.
Although this incident involved the use of an incorrect intersection rather than a wrong runway, a study conducted by the US Federal Aviation Administration in 2007, Wrong Runway Departures, outlines some relevant and important points. A class 2 electronic flight bag, which shows the aircraft’s location on a moving map display, is a technological enhancement described in the study as a safety enhancement to mitigate the risk of aircraft taking off from a wrong runway. The study identified a number of factors that contributed to aircraft taking off from an incorrect runway including:
a similar layout, with one taxiway leading to an area with multiple runway thresholds located in close proximity to one another
a short distance between the airport terminal and the runway
a complex airport design
the use of a runway as a taxiway
a single runway that uses intersection departures.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 21 October 2016, the ATSB was advised that the United States National Transportation Safety Board (NTSB) had commenced an investigation into a collision with terrain involving a Ryan W. Gross Arion Lighting, registered N235SC.
As Australia is the State of Manufacture of the engine, the ATSB requested to be appointed as an accredited representative to the NTSB investigation in accordance with clause 5.18 of Annex 13 to the Convention on International Civil Aviation Aircraft Accident and Incident Investigation. An ATSB investigator was appointed as accredited representative to the NTSB. To facilitate support to the NTSB investigation, the ATSB also initiated an investigation under the Australian Transport Safety Investigation Act 2003.