In the early afternoon of 22 March 2021, a Piper PA‑31P‑350 Mojave aircraft, registered VH-XGW, departed Dubbo Airport, New South Wales (NSW), for a flight conducted under the instrument flight rules to Bankstown Airport, NSW, with one pilot and a crew member on board.
On arrival at Bankstown, the pilot commenced a GPS instrument approach for runway 11C. While the initial part of the approach proceeded normally, the aircraft was observed by the Bankstown tower controller to track 0.5 NM (0.9 km) to the south of the required track, and this was advised to the pilot. After the aircraft passed the final approach fix, due to continued deviation, the tower controller instructed the pilot to discontinue the approach.
The pilot initially acknowledged that instruction but then requested, and was approved by the controller, to continue the approach visually as the aircraft had descended clear of cloud. The pilot then conducted extensive manoeuvring, including two orbits, at low altitude that were not in accordance with the approach requirements, before landing the aircraft safely on runway 11C.
What the ATSB found
The ATSB identified that, while conducting an instrument approach into Bankstown Airport in instrument meteorological conditions, the pilot did not conduct a missed approach when the aircraft exceeded the tracking tolerance limits. That resulted in the aircraft operating significantly below the minimum allowable altitude.
Additionally, having descended visually below the minimum descent altitude and commenced manoeuvring to position the aircraft for a landing at Bankstown Airport, the pilot did not conduct a missed approach when the aircraft exited the circling area and the required visual reference with the runway was lost.
Safety message
Managing approaches is one of the ATSB’s SafetyWatch priorities. Adherence to operational procedures ensures consistency of pilot action and aircraft operation during the approach and landing phases of flight. This, along with careful monitoring of aircraft and approach parameters, ensures instrument approaches are conducted safely.
Most importantly, if the criteria for safe continuation of an approach are not met, the pilot should conduct a missed approach to negate the risk of colliding with obstacles or terrain.
The investigation
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 22 March 2021 the pilot of a Piper PA-31P-350/A1 Mojave, registered VH-XGW (Figure 1) conducted pre-flight preparations for an early afternoon flight from Dubbo, New South Wales (NSW), to Bankstown, NSW. The flight was to preposition the aircraft at Bankstown for a medical transport flight planned for later that day. The crew for the flight from Dubbo comprised the pilot and a flight nurse. The aircraft was fitted with a Global Positioning System (GPS)[1] navigation unit and autopilot.
Figure 1: VH-XGW
A photo of VH-XGW.
Source: JETPHOTOS, Kynan Schneider
The aerodrome forecast for Bankstown,[2] which was obtained by the pilot and covered the period from 1100 Eastern Daylight‑saving Time[3] through to 2200, stated that the expected visibility was greater than 10 km with light rain showers and scattered[4] cloud at 1,500 ft above mean sea level (AMSL) and broken cloud at 2,500 ft.
The forecast included temporary changes, where visibility would reduce to 3,000 m in moderate rain showers and the cloud cover would include a broken layer at 800 ft. Having reviewed the forecast and other planning data, the pilot submitted a flight plan, which stated that the flight’s planned duration was 58 minutes, the aircraft had an endurance in excess of 4 hours, and that the flight would be conducted under instrument flight rules (IFR).[5] The flight plan also stated that the aircraft was performance category B (CAT B) (see the section titled Circling area).
At 1343, the aircraft departed Dubbo for Bankstown. As the aircraft approached Bankstown, the pilot was cleared to conduct an RNAV-Z(GNSS)RWY11C (RNAV-Z) instrument approach procedure into Bankstown (see the section titled Bankstown RNAV-Z approach). At 1448, the pilot called Bankstown tower and reported approaching the RNAV-Z intermediate approach fix at an altitude of 2,500 ft. In response, the tower instructed the pilot to report at the final approach fix (SBKWF). At this point in the flight the aircraft was in cloud. The pilot reported that the approach into Bankstown was predominantly flown with the use of the aircraft’s autopilot.
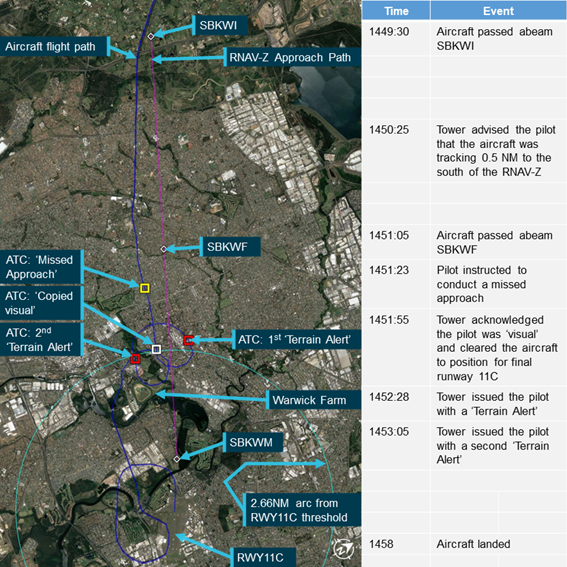
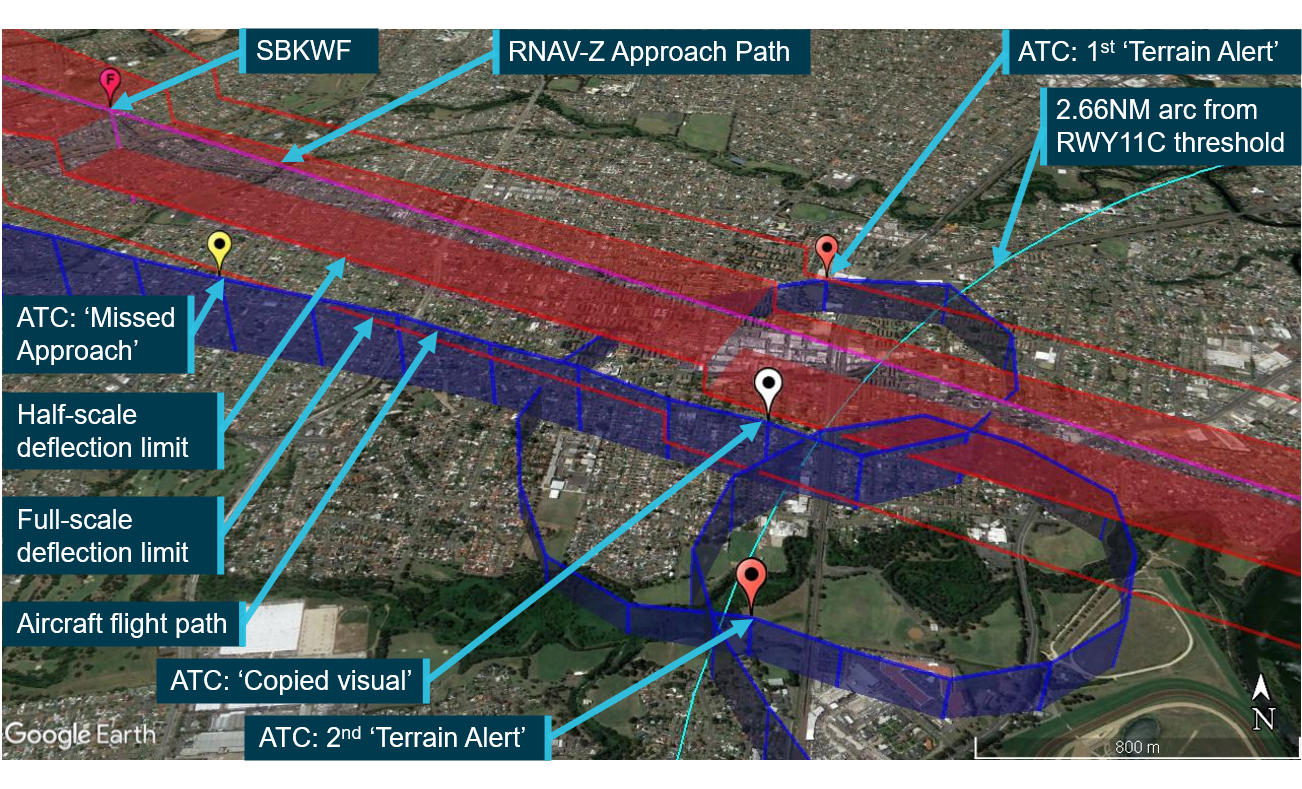
Figure 2 shows the aircraft’s flight path[6] in relation to the RNAV-Z instrument approach procedure’s required track. The aircraft passed abeam the intermediate approach fix (SBKWI) at 1449:30 and then began diverging from the RNAV-Z approach path as it tracked towards the final approach fix (SBKWF). Approaching SBKWF, the tower advised the pilot that the aircraft was tracking 0.5 NM (0.9 km) to the south of the approach path and enquired whether aircraft operations were normal. The pilot responded that operations were normal.
After the aircraft passed abeam SBKWF, the tower instructed the pilot to conduct the missed approach due to the continued significant deviation from the expected flight path. The pilot responded, ‘going around’–at that time the aircraft was descending through 1,100 ft. Despite the pilot advising the intention to commence the missed approach, further communications then ensued, during which the pilot requested to conduct a circling approach. In response the tower enquired about whether the pilot was visual, and the pilot advised that they were. The aircraft continued to descend and track towards the runway. About 30 seconds after the pilot called ‘going around’, the tower acknowledged the pilot’s ‘visual’ declaration and instructed the pilot to join final for runway 11C.
Figure 2: Aircraft flight path in relation to the RNAV-Z track and related key events
A Google Earth image of the aircraft’s approach track with significant events and locations marked.
Source: Google Earth and Airservices Australia, modified by the ATSB.
The pilot advised that, on receipt of the amended tracking instruction from the tower, they checked the GPS distance readout and confirmed that the aircraft was established within the CAT B circling area. Shortly after, the pilot stated that the aircraft entered a rain shower and visibility was momentarily reduced. To retain visual flight conditions, the pilot initiated a sharp left turn. Also, at about this time, the tower cleared the aircraft to land, which the pilot read back.
At 1452:28, as the aircraft was observed to be tracking away from the runway and at an altitude of 500 ft, the tower issued a safety alert for terrain to the pilot, which the pilot acknowledged. The tower followed this up with confirmation that the QNH[7] was 1019 (hPa), which the pilot read back. The aircraft continued the left turn to complete a full left orbit. During this orbit, the aircraft descended to an altitude of 400 ft as it crossed the RNAV-Z approach path the second time tracking south. The terrain elevation in that area is about 100 ft.
At 1453:05, as the aircraft exited the orbit to the west of the Warwick Farm racecourse at an altitude of 500 ft, the tower issued a second safety alert for terrain as they had lost sight of the aircraft. The pilot responded that the aircraft was over the Georges River (adjacent to Warwick Farm racecourse) and manoeuvring. Shortly after, the tower advised the pilot that they had regained sight of the aircraft.
The pilot then commenced a second left orbit at an altitude of between 5-600 ft. During this second orbit the tower requested confirmation that the pilot had the aerodrome in sight. The pilot responded in the affirmative, and that the intention was to ‘sort some things out’ while over the racecourse. The tower then instructed the pilot to join final, track as required and report established on final. The pilot acknowledged the instruction. The aircraft had, by then, completed the second orbit and commenced tracking towards the aerodrome. Shortly thereafter, the tower provided further advice concerning weather to the north of the airfield. In response, the pilot positioned the aircraft for a right circuit to runway 11C and landed at 1458.
The pilot later reported that the aircraft performed normally during the flight and that there were no faults with the aircraft or it’s navigation systems.
Context
Instrument approach requirements
Aeronautical Information Publication (AIP) ENR 1.1 paragraph 2.11.2.1[8] provided that, unless authorised to make a visual approach, an IFR flight must conform to the published instrument approach procedure nominated by air traffic control (ATC). A pilot can request ATC authorisation to deviate from an instrument approach procedure, and that subsequent authorisation is deemed an instruction from ATC.
The Bankstown automatic terminal information service (ATIS)[9] information valid at the time of the occurrence identified that an instrument approach procedure was required for the approach and landing into Bankstown. The relevant components of the information were that:
runway 11C was in use
instrument approach procedures were in place
visibility was 8,000 m, reducing to 3,000 m in rain showers
cloud comprised few at 1,000 ft, scattered at 2,000 ft and broken at 3,000 ft
the QNH was 1019 hPa.
Bankstown RNAV-Z approach
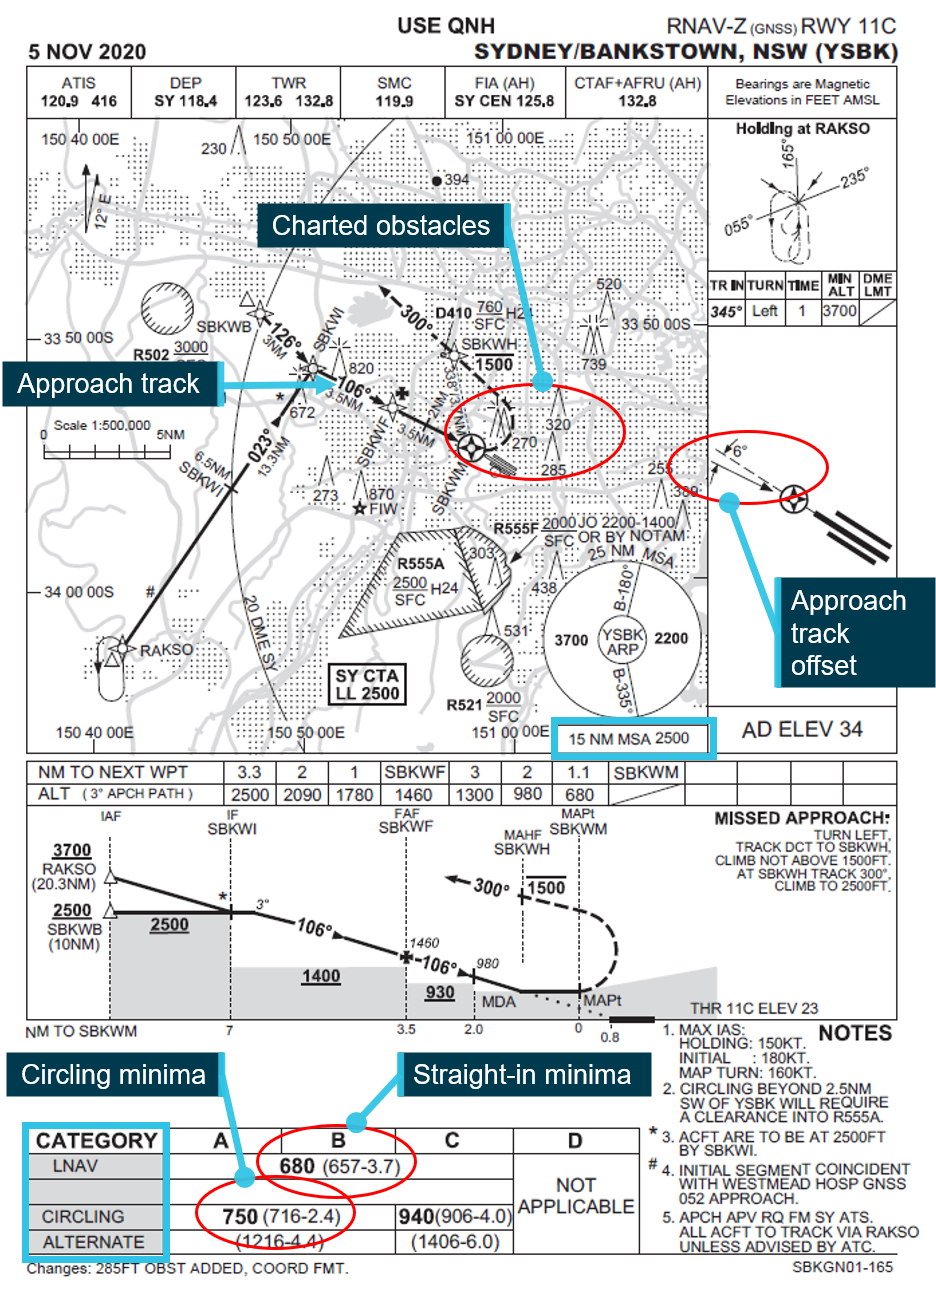
The RNAV-Z(GNSS)RWY11C approach procedure (Figure 3) is a non-precision approach (NPA) that uses GNSS signals for a 2-dimensional instrument approach procedure. The following features from the chart are relevant to the approach:
The approach is designed as a straight-in approach to runway 11C, with the option of conducting circling approaches to the airport’s runways.
The minima titles are shaded. This identifies that the published minima could be reduced by 100 ft when using an actual QNH, such as that provided by the Bankstown ATIS.
The approach minima, based on the aircraft’s performance category CAT B[10] as reported in the flight plan, were:
for the straight-in approach, the minimum descent altitude (MDA) of 580 ft AMSL
for the circling approach, the MDA of 650 ft AMSL.
The plan profile of the chart identified several obstacles around the approach and missed approach track. The highlighted obstacles had the potential to directly affect the approach and/or missed approach flight paths when below the approach minima.[11]
The minimum safe altitude within 15 NM of Bankstown Airport was 2,500 ft AMSL.
Figure 3: The RNAV-Z(GNSS)RWY 11C approach procedure chart
Source: Airservices
The circling area
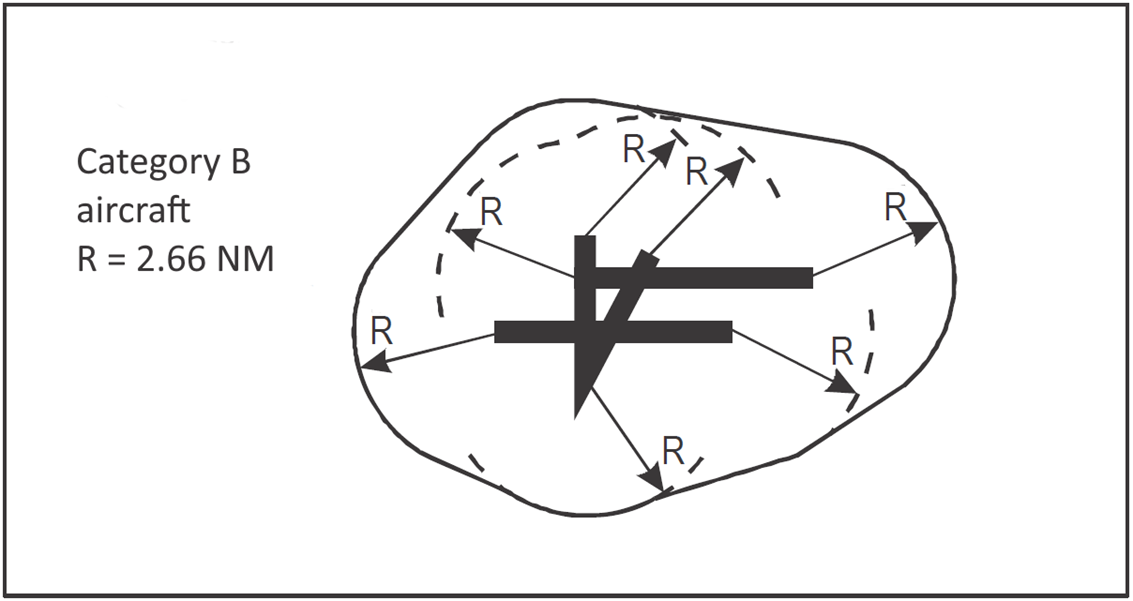
The required obstacle clearance for circling approaches is established by applying a radius distance, which is based on the aircraft’s performance category, to the threshold of all runways usable by that category of aircraft. For a CAT B aircraft, that radius is 2.66 NM. Tangents are then drawn from the extremities of the arcs to complete the circling area (Figure 4). The circling minima is then determined by applying the required obstacle clearance value of 90 m, or approximately 300 ft, to the highest obstacle within that area.
The pilot reported that, during the conduct of the instrument approach and the subsequent visual manoeuvring, an available option was to remain inside the higher CAT C circling limits (based on a radius of 4.2 NM) and above the required obstacle clearance limit of 400 ft.
The pilot also stated that at no time was the aircraft’s barometric altimeter observed to go below 400 ft. However, with an accurate QNH set, that instrument measures height AMSL within defined accuracy tolerances. Consequently, operating at an altitude of 400 ft within the CAT C circling area for Bankstown Airport did not provide the required terrain clearance as it did not allow for the terrain elevation and obstacles.
Figure 4: CAT B circling area construction
Source: ICAO Doc 8168 Volume II.
Approach tolerances for the RNAV-Z approach
The following lateral approach tolerances applied to the RNAV-Z approach into Bankstown Airport:[12]
For the intermediate segment of the approach, the required navigation performance (RNP)[13] is 1.0 NM, which is displayed as full-scale deflection on a course deviation indicator (CDI)[14] to the pilot. The target level of safety performance for this segment is within half‑scale CDI deflection—that is 0.5 NM.
From 2 NM before the final approach fix, the GPS tracking display transitions to the final segment RNP of 0.3 NM, displayed as full‑scale CDI deflection. The target level of safety performance for the final segment is also half-scale CDI deflection—that is 0.15 NM.
Under Civil Aviation Order 20.91,[15] a missed approach must be executed if, during the segment of a procedure, the cross-track error/deviation equals or is reasonably likely to equal, the RNP for segment of the procedure.
The aircraft’s GPS unit automatically sets the aircraft navigation instruments’ CDI scale to the RNP limits for the various segments of the RNAV-Z procedure as described above.
An aircraft must be ‘established’ on the instrument approach procedure’s track before commencing descent on the approach procedure.[16] Established was defined as within half-scale deflection for GNSS type approaches.
Application of the approach tolerances to the occurrence flight path
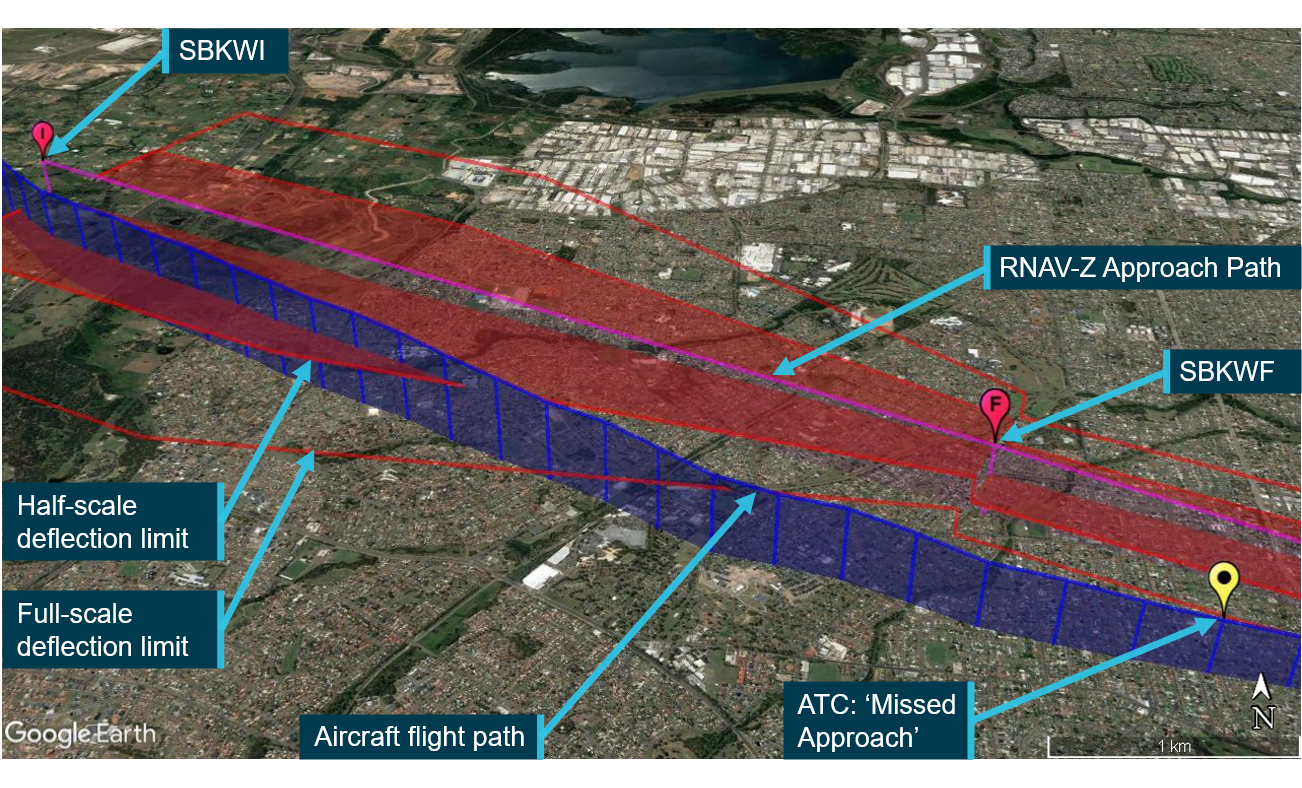
The aircraft’s flight path with respect to the approach tolerances is displayed in Figure 5. The half‑scale and full-scale limits are displayed as a surface set to the segment’s minimum segment altitude of 1,400 ft. while the full-scale tracking limits are displayed as the outer red line. The transition from the intermediate segment’s RNP 1.0 NM to the final segment’s RNP 0.3 NM is displayed as a progressively decreasing maximum permissible displacement (decreasing tolerance) from 2.0 NM before final approach fix (SBKWF).
The aircraft’s track early in the intermediate approach segment was within tolerances, but progressively diverged from the required approach path. The decreasing tolerance from 2 NM before SBKWF and the divergent flight path resulted in the aircraft rapidly exceeding the required tracking tolerances for the intermediate segment. It was at around this point in the approach that the tower alerted the pilot to the aircraft tracking 0.5 NM south of the required instrument approach path. As the aircraft passed abeam SBKWF, it was significantly outside of the full-scale RNP limit at an altitude of 1,400 ft.
Figure 5: The aircraft’s initial approach flight path in relation to tracking tolerances
Source: Google earth and Airservices, modified by ATSB.
The aircraft’s flight path with respect to the approach tolerances in the final approach segment is displayed in Figure 6. After passing abeam the final approach fix the aircraft’s lateral displacement from the required approach track exceeded the full‑scale RNP limit.
During the final approach segment, the aircraft’s track converged with the required track, but the aircraft was not established within the required tracking tolerances until after the pilot reported being visual to ATC.
At the commencement of the left orbit, and as the aircraft crossed the approach track for the first time, the aircraft was above the straight‑in approach minimum descent altitude of 580 ft. As the orbit continued and the aircraft crossed the approach track for the second time, the aircraft was below the 930 ft segment minimum altitude and had descended below the 580 ft approach minimum descent altitude. The aircraft was also outside of the CAT B circling area (represented by the light blue arc).
Figure 6: The aircraft’s final approach flight path in relation to tracking tolerances
Source: Google earth and Airservices, modified by ATSB
Missed approach requirements
AIP ENR 1.5 paragraph 1.10.1[17] contained specific circumstances where a missed approach must be conducted. These included:
during the final segment of an instrument approach, where the aircraft is not maintained within the applicable navigation tolerance for the aid in use
when the required visual reference is not established at or before reaching the missed approach point from which the missed approach procedure commences
when a landing cannot be made from a runway approach, unless a circling approach can be conducted in weather conditions equal to or better than those specified for circling
when visual reference is lost while circling to land from an instrument approach.
In a note following these requirements, ‘visual reference’ was defined as meaning the runway threshold, or approach lights or other markings identifiable with the landing runway were clearly visible to the pilot, and for circling approaches, clear of cloud, in sight of the ground or water and with a flight visibility not less than the minimum specified for circling.
Descent from the minimum descent altitude to the runway
The aim of an instrument approach procedure is to position the aircraft so that the pilot can establish visual contact with the runway and land. The AIP detailed the requirements for the transition from the instrument approach procedure and descent from the MDA to positioning for a landing. These requirements varied depending on whether a straight-in approach or a circling approach was being conducted.
Straight-in approach
For a straight-in approach, AIP ENR 1.5 paragraph 1.8.2[18] stated that, provided the required meteorological minima are met, descent below the straight-in MDA may only occur when:
visual reference can be maintained and
the aircraft is continuously in a position from which a descent to a landing on the intended runway can be made at a normal rate of descent using normal flight manoeuvres that will allow touchdown to occur within the touchdown zone of the runway of intended landing.
The definition of ‘visual reference’ in this context is the same as previously detailed in the section titled Requirements for a missed approach.
Circling approach
The circling approach and visual circling rules are more complex than those for the straight-in approach. The following components of these rules are relevant:[19]
During visual circling, descent below the circling MDA may only occur when the pilot
a. maintains the aircraft within the circling area; and
b. maintains a visibility, along the intended flight path, not less than the minimum specified on the chart for the procedure; and
c. maintains visual contact with the landing runway environment (i.e. the runway threshold or approach lighting or other markings identifiable with the runway); and either ...
e. in daylight only, while complying with a., b. and c., maintains visual contact with obstacles along the intended flight path and an obstacle clearance not less than the minimum for the aircraft performance category until the aircraft is aligned with the landing runway.
Notes that followed these rules stated the following:
Note 1: The concept is as follows: ...
(2) When daylight exists and obstacles can be seen, the pilot has the option of descending from MDA from any position within the circling area while maintaining an obstacle clearance not less than that required for the aircraft performance category.
(3) Once the pilot initiates descent below circling MDA, the obstacle protection offered by visual circling at the MDA ends and they are responsible for ensuring the required clearance from obstacles is maintained visually.
Guidance on non-precision approaches
The Civil Aviation Advisory Publication (CAAP) 178-1(2)[20], provided guidance on the conduct of an NPA, such as the Bankstown Airport RNAV‑Z approach. The CAAP compiled all relevant regulation, standards, and practices into a single document, but also recommended that it be read in conjunction with those sources.
Straight-in approach
The CAAP stated that it is commonly acknowledged that straight-in approaches are significantly safer than circling approaches. For an NPA with a straight in approach, once the criteria for descent from the MDA are met, the required approach path from the MDA to the runway is protected from obstacles by aerodrome and instrument procedure design standards. The visibility requirement for the straight-in approach is based on the distance from the runway threshold where a normal 3-degree approach descent path to the runway intercepts the MDA.
Circling approach
Circling approaches normally require manoeuvring to align the aircraft with a suitable runway other than the designated straight‑in runway. Circling is a visual procedure that can be hazardous if not executed correctly. Visibility for circling operations is based on the relevant aircraft category’s radius of turn, in adverse wind conditions, to enable the aircraft to manoeuvre from a downwind position and align with the landing runway.
This visibility value will most likely be less than that required for a straight-in approach. This is due to the normal profile for the circling approach, which is to remain at or above the circling MDA until the aircraft is established within the aerodrome’s circuit area, and then to visually circle for landing within the circuit while maintaining visual contact with the runway. Obstacle clearance is guaranteed in the normal runway circuit pattern.
The pilot may elect to descend below the circling MDA by day, but only in accordance with specific rules. In doing so the pilot takes responsibility for obstacle clearance. As spot heights on instrument approach and landing charts do not necessarily indicate the highest terrain, or all obstacles in the circling area, pilots should only exercise this option when they are familiar with the terrain in the circling area. Without detailed local knowledge, it is a safer option to utilise the obstacle protection afforded by remaining at the circling MDA until within the circuit area.
Safety analysis
On the afternoon of 22 March 2021, the pilot of VH-XGW commenced a flight from Dubbo to Bankstown. The flight was conducted under instrument flight rules and, due to the prevailing weather conditions, an instrument approach procedure was necessary to enable a landing at Bankstown Airport.
Tracking tolerance exceedance
The ATC clearance for the approach into Bankstown required the conduct of a straight-in instrument approach to runway 11C. As the aircraft passed abeam the intermediate approach fix, the aircraft was within the required half-scale deflection to be established on the approach path, enabling the pilot to commence descent on the approach. However, from that point on the aircraft progressively diverged from the required track.
Approaching abeam the final approach fix, the combination of reducing track tolerance and continued track divergence resulted in the aircraft exceeding the tolerance limit of full-scale deflection, or 0.3 NM track displacement. Significantly, this tracking error resulted in the aircraft being displaced outside of the area that had been surveyed to be clear of obstacles at an altitude of 1,100 ft, well below the Bankstown 15 NM minimum safe altitude of 2,500 ft. Further, the pilot reported that, at this point in the approach, visual flight conditions had not yet been established.
Despite those circumstances, the requirements of the instrument approach and the ATC instruction, the pilot did not conduct the published missed approach procedure.
Descent below the minimum descent altitude
Following initial acknowledgement of the ATC missed approach instruction, the pilot requested a clearance for a circling approach while continuing the descent. During the ensuing 30 seconds of communications, the aircraft descended out of the cloud and the pilot reported being visual to ATC. The pilot also advised that they checked the distance readout to Bankstown Airport and confirmed that the aircraft was within the aerodrome CAT B circling area.
At about the same time, ATC cleared the aircraft to track for final runway 11C. The pilot then initiated descent from MDA at the CAT B circling boundary with the intention of maintaining visual contact with obstacles along the intended flight path at the minimum permitted obstacle clearance height. The pilot considered that this was the safest option, given the weather conditions and the aircraft’s absence of a weather radar.
Such manoeuvring at that position was contrary to the intention of a circling approach, which is normally performed within the surveyed environment of the circuit area as part of visual circling to other than the straight‑in approach runway. More importantly, when compared to the straight-in approach descent profile, it resulted in reduced obstacle clearance, increased pilot workload and an increased risk of an unstable approach.
Loss of visual reference while below MDA
Shortly after entering the CAT B circling area, and with the pilot having reportedly established visual contact with the runway environment, the aircraft entered a rain shower. To maintain visual flight conditions, the pilot commenced a left turn away from the runway. This turn continued in to the first of two left orbits, during which the aircraft exited the CAT B circling area and descended to an altitude of around 400 ft.
The pilot stated that the aircraft was maintained within the larger CAT C circling area and that the required separation with obstacles was maintained. However, flight surveillance data indicated that the aircraft descended below the minimum altitude required to maintain separation from the terrain below the aircraft. Further, ATC was expecting the aircraft to operate within the CAT B circling limits, as stated in the flight plan, and twice during the conduct of the orbits provided terrain alerts to the pilot.
When operating below MDA, collision with terrain or obstacles are the immediate threat. The AIP and CAAP 178 stated that not all terrain and obstacles are marked on aerodrome charts. Further, the only areas where obstacle clearance is assured are those associated with the straight-in approach path, and within the circling area. Outside of these areas, separation from terrain and obstacles while below the MDA is dependent on visual acquisition and avoidance. Additionally, continuation below MDA is predicated on the pilot continuously maintaining visual reference with the runway.
Almost immediately on declaring visual, visibility deteriorated sufficiently for the pilot to initiate a turn away from the runway. The pilot stated that visual reference was only lost momentarily, however, during the left turns away from the airport, the runway environment would have been obscured by the aircraft’s structure for significant periods of time. Despite that, the pilot persisted with the approach and landing rather than conducting the published missed approach. Continuation of the approach resulted in the loss of obstacle clearance assurance and an increased risk to the aircraft occupants.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the flight below minimum safe altitude by VH-XGW on 22 March 2021.
Contributing factors
While conducting an instrument approach into Bankstown Airport in instrument meteorological conditions, the pilot did not conduct a missed approach when the aircraft exceeded the tracking tolerance limits. That resulted in the aircraft operating significantly below the minimum allowable altitude.
Having descended visually below the minimum descent altitude and commenced manoeuvring to position the aircraft for a landing at Bankstown Airport, the pilot did not conduct a missed approach when the aircraft exited the circling area and the required visual reference with the runway was lost.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot
Civil Aviation Safety Authority
AIRMED Australia Pty Ltd
Airservices Australia.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the pilot
Civil Aviation Safety Authority
AIRMED Australia Pty Ltd
Airservices Australia.
Submissions were received from:
the pilot
Civil Aviation Safety Authority.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
In the early hours of 25 March 2021, a fire broke out in the lower cargo hold of the general cargo ship BBC Rhonetal while it was alongside Port Hedland number two berth. The fire started during hot work to remove sea fastenings from the tween deck in preparation for cargo discharge operations.
Immediate efforts by the crew to extinguish the fire with deck hoses were unsuccessful and all persons safely evacuated the area before the hatch covers were closed and carbon dioxide using the ship’s fixed fire extinguishing system was released into the cargo hold. Shoreside fire authorities responded to the emergency and monitored the situation until the fire was declared extinguished on the morning of 28 March.
What the ATSB found
The ATSB found that the risk of fire had not been adequately assessed by the crew prior to commencement of the hot work. As a result, a continuous fire watch was not maintained and proper precautions were not taken to sufficiently protect vulnerable cargo from catching alight.
The ATSB also found that BBC Rhonetal’s managers had not effectively implemented the shipboard safety management system procedures to prevent the fire, which was the tenth such fire on a ship managed under the same parent company in the past 14 years, and the fourth investigated by the ATSB, identifying similar contributing factors.
What has been done as a result
BBC Rhonetal’s managers advised the ATSB that shipboard procedures for hot work will be amended to better describe the fire watch role, emphasising its importance in fire prevention. Fire watch requirements will be integrated into the hot work permit procedure and additional equipment for the fire watch is to be distributed across the fleet. The company also intends to educate ship crews on the amended procedures and the additional equipment through a training video with shore-based staff further reiterating safe hot work practices during shipboard inspections.
The ATSB considers that the proposed safety action has the potential to address the safety issue concerning the hot work procedures. However, as no timeline for implementation was provided, the ATSB issued formal recommendations to BBC Rhonetal’s managers, and the parent company, that the proposed safety action be implemented across their fleets.
Safety message
The continuing incidence of fires in the cargo holds of ships while performing hot work highlights the importance of adhering to shipboard procedures and recognised safe work guidelines for hot work.
Ship operators and managers must ensure that their safety management system protocols for hot work are suitable and properly implemented on board their ships. This requires regular verification that ships’ crew understand and follow prescribed safe work practices for hot work.
The occurrence
Overview
At 0420 Australian Western Standard Time[1] on 24 March 2021, the geared general cargo ship BBC Rhonetal (Cover image) berthed at number two berth in Port Hedland, Western Australia. The ship was to discharge cargo which consisted of project cargo[2] and large metal structures of various shapes and sizes.
While the ship had been at sea, the cargo had been lashed to sea fastenings; metal D-ring brackets that had been welded to the ship’s cargo areas at various locations to keep it from shifting (see the section titled Cargo securing arrangements). These fastenings needed to be removed through hot work such as cutting and gouging before the cargo could be discharged.
After arriving, the ship’s chief mate convened a safety meeting at 0430 to discuss removal of the sea fastenings using a plasma torch and to review the existing hot work risk assessment and procedure.[3] This 10-minute meeting was attended by the master, chief mate, second mate, a junior officer, the bosun, two ordinary seaman (OS), two able seaman and two deck cadets. A safety meeting form was printed out and each crew member signed it to confirm their attendance. The chief mate then issued a hot work permit which was to commence at 0500 and remain in effect for the following 24-hour period.
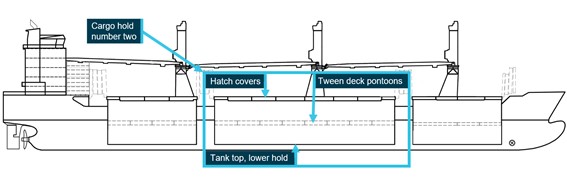
At about 2358 on 24 March, the bosun and an OS, along with the second mate as supervisor, arrived on deck to assume the cargo watch. Shortly after, they started preparations as planned to cut the sea fastenings. In anticipation of this hot work, several crew members on the earlier watch had opened the hatch covers to number two cargo hold and prepared firefighting equipment on the tween deck in the hold (Figure 1).
Figure 1: Profile view of BBC Rhonetal
Source: Briese Schiffarhts, modified and annotated by the ATSB
The firefighting equipment included three fire hoses which were pressurised (using the ship’s fire main line) and ready for immediate use by opening their fire nozzles. There were also two fire extinguishers, two spark arrester drums and four fire blankets close by. The fire blankets each measured about 2 m in length and were to be used to cover the gaps in the tween deck (Figure 2) near the work areas to prevent sparks and molten metal produced by the cutting work from falling through to the lower hold.
Figure 2: Tween deck gaps
Source: Pilbara Ports Authority
Cargo in the lower hold consisted of various metal structures as well as two large, linear vibrating screen assemblies with rubber internal components. The assemblies were located in the aft section of the hold and had been wrapped in protective plastic coverings for shipping (Figure 3).
At 0030 on 25 March, the bosun began using the plasma torch to remove sea fastenings at the forward end of the tween deck. The cutting gradually progressed towards the aft end of the deck. Stevedores followed the bosun’s progress aft, using the ship’s crane to discharge items of cargo as the fastenings were removed. Meanwhile, the OS maintained a fire watch in the lower hold, directly below the hot work progressing on the tween deck. He was ready with a fire extinguisher, two buckets of water, a flashlight and a handheld radio. During this time, the OS saw sparks from the plasma cutting above falling into the lower hold and extinguishing before reaching the bottom of the hold. As the work continued, the second mate remained on the tween deck to supervise and oversee both the hot work and the cargo operations.
At about 0250, the bosun called the OS using a handheld radio and instructed him to conduct a final inspection of the lower hold and then go to the tween deck to assist with removing the sea fastenings. At 0300, having checked that there were no sparks or signs of fire in the lower hold, the OS started working at the forward part of the tween deck, using a grinder to remove remnants of the fastenings left after the plasma cutting.
Meanwhile, the bosun continued using the plasma torch and had progressed to the aft part of the tween deck, located above the plastic-wrapped screen assemblies in the lower hold below. At that time, sparks from the plasma cutting were spreading across a broad area. A smaller quantity of sparks was also generated by the grinding work forward (Figure 3).
Figure 3: CCTV images of the hot work with the locations indicated on the stowage plan
Source: Briese Schiffahrts and Pilbara Ports Authority, modified by the ATSB
At 0309, the second mate on the tween deck saw smoke rising from the aft part of the lower hold. The smoke intensified quickly and began billowing over the cargo hold and the wharf (Figure 4). The stevedores also saw the smoke and quickly left the ship, leaving behind an item of cargo on the tween deck connected to the crane hook in preparation for discharge.
Figure 4: Intensifying smoke from the lower hold (CCTV frames at 0309 and 0310)
Source: Pilbara Ports Authority, annotated by ATSB.
The second mate, bosun and OS immediately directed water towards the area where the smoke was rising using the available fire hoses. Shortly after, they also saw flames coming through gaps in the tween deck.
At about 0312, the second mate rushed up to the navigation bridge, sounded the general alarm and made an announcement on the public address system. At about the same time, Port Hedland vessel traffic service (VTS) received a telephone call from security personnel on the wharf reporting the fire. At about 0315, the master and chief mate arrived on the bridge, and the master called VTS via VHF radio and requested harbour tugs to assist the firefighting efforts.
The crew’s attempts to extinguish the fire with hoses were unsuccessful, so the master ordered them to evacuate the hold, intending to use the ship’s fixed carbon dioxide (CO2) extinguishing system for the holds. The hatch covers, however, could not be closed due to the cargo connected to the crane’s hook. A short time later, the chief mate, wearing a self-contained breathing apparatus, climbed up to the crane operator cabin and landed the cargo onto the wharf.
Meanwhile, three harbour tugs had arrived and began directing water on to the ship for boundary cooling (Cover image). At 0337, firefighters from local units of the Western Australia Department of Fire and Emergency Services (DFES) also arrived.
At 0410, on the master’s orders, the ship’s crew closed the hatch covers and then released carbon dioxide into the hold. At about this time, the second mate began feeling unwell due to smoke inhalation and was taken to hospital (he was treated and discharged shortly afterwards).
Later that day, at 1530, a DFES contingent from Perth arrived to assist with the response, including planning entry to the hold for inspection and assessment.
Over the following 2 days, firefighters conducted routine monitoring of the temperatures and CO2 levels inside the hold. The tugs continued boundary cooling along the ship’s hull.
In the early hours of 27 March, DFES personnel entered the hold and reported that the fire appeared to have been extinguished. Following the assessment, they started ventilation by partially opening the hatch covers and stopped the boundary cooling.
Post-fire damage assessment
At 0804 on 28 March, DFES firefighters declared the fire extinguished. Post-fire inspections identified that the fire started on one of the linear vibrating screen assemblies stowed in the lower hold, directly below where the bosun was last seen plasma cutting before the smoke and flames were sighted (Figure 5).
Figure 5: Burnt remains of the vibrating screen assembly
Source: Western Australia Department of Fire and Emergency Services
The fire destroyed the vibrating screens. Photos taken after the fire showed that the intense heat from the blaze had left scorch marks on surrounding areas in cargo hold number two and on several items of cargo on the tween deck above the fire. The firefighting efforts had resulted in the accumulation of 600 cubic metres of water in the bottom of the hold. This wastewater was transferred into the ship’s water ballast tanks and later disposed of in compliance with marine pollution prevention regulations.
The ship remained in Port Hedland until 22 April to complete its cargo operations and to await the Australian Maritime Safety Authority’s confirmation of the ship’s seaworthiness.
BBC Rhonetal is a 161.5 m, multi-purpose, heavy-lift, general cargo ship registered in Antigua and Barbuda. The ship was built in 2013 by Taizhou Sanfu Ship Engineering, China and classed with DNV GL. It has three cargo holds with tween decks and can carry containers and/or general cargo. Each of the ship’s three cranes have a SWL of 80 t and two cranes can be used in tandem to lift loads up to 350 t.
At the time of the fire, BBC Rhonetal was owned by Briese Schiffahrts, managed by Briese Heavylift and operated by BBC Chartering & Logistic, all of Leer, Germany. Briese Schiffahrts[4] (Briese), the parent company, was established in 1984 and at the time of the fire was one of the largest providers of heavy-lift ships to transport project cargo. Briese and its subsidiary companies provide ship and crew management, chartering and other services. The company’s ship management arm was restructured in 2018, when Briese Heavylift[5] was formed to manage larger geared cargo ships.
The ship’s multi-national crew of 21, including the master, comprised Russians, Ukrainians, and Filipinos The master had 20 years of seagoing experience and held a Russian master’s certificate of competency, issued in 2007. Most of the master’s seagoing experience was on board Briese general cargo ships. He first joined BBC Rhonetal in March 2020 and sailed for one voyage as chief mate before re-joining the ship as master in November 2020 for another assignment.
The chief mate had 14 years of seagoing experience, including 5 as chief mate, and held a Russian master’s certificate of competency. All the chief mate’s experience had been gained on Briese bulk carriers and general cargo ships. The chief mate joined BBC Rhonetal for the first time on 27 October 2020.
The second mate had 10 years of seagoing experience and held a Russian chief mate’s certificate of competency. All the second mate’s experience had been on board Briese bulk carriers and general cargo ships. The second mate had also joined BBC Rhonetal on 27 October 2020 for the first time.
The bosun had 29 years of seagoing experience. He was also a qualified welder and the only crew member on board BBC Rhonetal trained to use the plasma cutting equipment. The bosun had worked on various types of ship in different companies during his career, including Briese, and joined BBC Rhonetal for the first time in October 2020.
The ordinary seaman (OS) had 5 years of seagoing experience. Having started his seafaring career with Briese, all of the OS’s seagoing experience had been accrued aboard bulk carriers and general cargo ships. The OS had joined BBC Rhonetal for the first time on 10 October 2020.
Cargo securing arrangements
BBC Rhonetal typically transported project cargo, including large items of machinery and components destined for the mining sector. These generally heavy items had to be secured to avoid shifting during the sea passage.
The common method to secure the cargo was to weld steel D-shaped rings, called sea fastenings, at specific locations on the cargo decks and then tightly lash the cargo to these fastenings using chains and straps. This technique was usually used in addition to welding steel brackets or lugs (often referred to as sea stoppers) to the deck, and directly against items of cargo, to prevent movement across the deck while at sea (Figure 6).
Figure 6: Example of project cargo securing
Source: Online image at admmarinesurvey.co.uk
Since the fastenings and stoppers were welded to the deck, hot work techniques including cutting and gouging were required to remove them whenever the cargo was discharged. As a result of this type of cargo securing arrangement, hot work operations were much more frequent on this type of multi-purpose general cargo ship than on many other types of cargo ships.
Shipboard safety management system
The International Safety Management (ISM) Code provides an international standard for the safe operation of ships at sea.[6] Its objective is to ensure the prevention of human injury or loss of life and the avoidance of damage to the environment and to property.
To help achieve this objective, the ISM Code requires companies to develop, implement and maintain a safety management system (SMS) that provides policies, procedures, instructions and guidance for the safe performance of all shipboard operations and the management of identified risks to the ship, personnel and the environment.
Under the ISM Code, a company must ensure its SMS is effective by periodically confirming that all shipboard personnel have an adequate understanding of its content.
BBC Rhonetal’s safety management system (SMS) included the following procedures for hot work (with associated forms and tools):
procedure for hot work
procedure for risk assessments
general risk assessment form for hot work
permit to work form with a section for hot work
safety meeting form for general hot work tasks.
Procedure for hot work
The SMS manual on board BBC Rhonetal included a section dedicated to hot work. It contained a requirement that a risk assessment be completed and reviewed periodically. Before starting hot work when in port, written permission was to be obtained from the relevant port authority, and the duty officer notified. The procedure further required that a permit to work be completed for all hot work on board, including welding and flame cutting, except when such work was performed in the welding space of the engine room workshop.
The hot work procedure stated that the ship must ensure a proper fire watch and fire precautions in addition to agreed procedures with shore workers or contractors. The procedure also directed crew to further guidance in the Code of Safe Working Practices for Merchant Seafarers (COSWP)[7], available on all Briese ships, including BBC Rhonetal.
This COSWP identified hot work as a task which should normally be the subject of a permit to work, and recommended that:
Procedure for risk assessment
BBC Rhonetal’s SMS included a procedure covering the conduct and management of risk assessments. The SMS included general risk assessments that were reviewed and updated by Briese on an annual basis with the master and officers responsible for the periodic review of these assessments.
Ship’s staff were required to notify the company of any additional hazards and risk controls identified as part of their onboard reviews for inclusion in the assessments. The procedure noted that the risk assessment process was to be initialised before implementing new processes or non‑routine tasks, and while reviewing existing processes.
It also explained that the occurrence of hazardous events on board might indicate weaknesses in the way risks have been assessed or mitigated. It required that any risk assessment be reviewed before implementation, and then periodically, to ensure risk controls remained effective and adequate.
Risk assessment for hot work
The general risk assessment form for hot work stated that, based on the outcome of the assessment, appropriate control measures were to be put in place while taking into account any relevant guidance contained in company fleet circulars.
The hot work risk assessment form contained a pre-filled risk matrix with several hazard scenarios, corresponding risk, control measures and resulting residual risk.
Among those identified scenarios, the risk matrix documented the hazard of molten metal from hot work on deck falling between gaps in the tween deck into the hold below. The assessment identified that this could result in major consequences, such as a fire on the cargo or in the hold and damage to cargo and other equipment.
The risk assessment identified several measures to mitigate the risk of fire. The measures included the issue of a hot work permit, the need for a safety meeting (toolbox meeting) prior to the commencement of hot work and the use of fire mats, fire blankets and other precautions in accordance with company circulars issued in response to past fires on board Briese ships (see the section titled Similar occurrences).
The risk assessment also identified additional measures related to fire response training and use of correct firefighting equipment. The outcome of the combined controls was indicated on the risk assessment tool as being effective in reducing the risk of fire from ‘major’ to ‘moderate’.
On BBC Rhonetal’s arrival in Port Hedland, the risk assessment and its pre-filled hazards, risks and control measures were reviewed, in preparation for the cutting of sea fastenings. The risk assessment form allowed for the capturing and recording additional hazards, risks or controls identified through a review immediately before work. No additional risks or precautions specific to the location of the intended hot work and the relative position of flammable cargo in the lower hold were recorded on the risk assessment form.
Permit to work system
The permit to work form consisted of a checklist for different types of special work tasks subject to the permit to work system, including hot work. The hot work section contained a list of checks and precautions required for the issue of the permit, including a prompt to check that surrounding areas were clear of dangerous materials and protected from sparks and weld splatter (Figure 7).
Figure 7: Hot work checklist section from the permit to work form
Source: BBC Rhonetal
A work permit for the cutting of sea fastenings was prepared during the safety meeting and was to remain in effect from 0500 for the next 24 hours. The permit was still valid when the hot work in hold number two began, about 19 hours after it was issued.
All the checklist items were marked as complete on an electronic version of the permit. It was then printed to allow crew members to sign that they understood and were able to fulfil the requirements of the permit. The bosun signed off as the person in charge of the work and the second mate signed off as the person in charge of fire watch.
Safety meeting
It was general procedure to use a company training record form to record safety meetings. Different versions of the form had been previously prepared on a computer as templates for regular use. These contained safety information and guidance specific to various shipboard tasks.
The version used to record the safety meeting held on 24 March had been pre-completed as a template for safety meetings prior to general hot work. It included a bullet point list identifying general precautions related to hot work, pertaining primarily to matters such as toxic fumes and personal health. The form did not contain any reference to the risk of fires.
Another version of the training record form, which contained information more specific to the removal of sea fastenings, was also available as a template. However, it was not the version used to record the safety meeting.
Similar occurrences
The fire on BBC Rhonetal was the tenth fire incident attributed to hot work on a Briese ship since 2007. Four of these fires occurred in Australian ports, three of which were investigated by the ATSB (summarised below). On each occasion, cargo was ignited or damaged by sparks and molten material generated from hot work.
BBC Islander
On 14 August 2007, a fire broke out on board the general cargo ship BBC Islander while anchored off Dampier, Western Australia. The ship’s crew were cutting sea stoppers on a cargo hold hatch cover with an oxy-acetylene torch when a hole was inadvertently cut in the hatch cover resulting in sparks and molten metal falling into the hold below and igniting cargo.
The crew’s attempts to extinguish the fire by flooding the cargo hold with carbon dioxide proved unsuccessful, so the ship was berthed on 16 August, where shore fire services attended. It took 2 days to extinguish the fire and only after the hold was flooded with water, resulting in severe damage to the cargo and the ship.
The ATSB investigation, report MO-2007-245, found that the ship’s SMS procedures had not provided sufficient guidance to ensure the crew appropriately assessed the risks associated with removing sea stoppers from hatch covers. As a result, proper precautions were not taken by the crew and a fire watch was not established inside the cargo hold before the hot work started.
BBC Baltic
On 26 January 2012, a fire broke out in the number one cargo hold of the general cargo ship BBC Baltic while discharging cargo in Port Hedland. Contractors from a local engineering company were using oxy-acetylene equipment to remove sea stoppers in the ship’s hold when sparks from the hot work set alight a tarpaulin covering an item of cargo adjacent to the work site.
The workers swiftly evacuated the area leaving the oxy-acetylene equipment on the tween deck, which then caught fire resulting in a large fire ball. The fire was extinguished about an hour later by the ship’s crew using fire hoses, with the assistance of two harbour tugs and the local fire brigade.
The ATSB investigation, report MO-2012-002, found that the ship's crew had not properly considered and mitigated the risk of fire before the hot work started. Precautions listed in the ship’s hot work permit had not been taken and a toolbox meeting before the hot work was not held.
As a result of the inadequate risk assessment, there was no fire watch in place, none of the ship's crew were at the hot work site and there was no clear understanding of the action to take in case of a fire.
In response to that fire, Briese advised that it had reviewed shipboard procedures for hot work with resulting improvements focused on the hot work permit system to ensure better coordination with shore workers through a toolbox meeting to identify risks, controls and responsibilities.
BBC Xingang
On 11 December 2017, a fire occurred aboard, BBC Xingang, while alongside in Newcastle, New South Wales. The incident occurred during the removal of sea stoppers from the tween deck by workers from a local engineering company using oxy-acetylene equipment. Sparks and molten metal generated by the hot work burned through protective fire mats covering gaps in the tween deck and onto unprotected cargo in the lower hold, resulting in the fire.
The fire watch was alerted to the fire over the radio by one of the contract workers who had seen smoke rising from the hold. The fire watch rushed to the location of the fire and quickly extinguished it using a water hose.
The ATSB investigation, report MO-2017-011, found that the flammable material covering the cargo in the hold below had not been identified as a fire risk and had not been adequately protected prior to the work commencing. Further, the fire watch had not been directed to closely monitor immediately below the work site and was not in position to quickly react when the cargo caught on fire.
As a result of the fire aboard BBC Xingang, Briese provided the ship with replacement fire blankets and convened a safety meeting on board the ship to review the circumstances of the incident. BBC Chartering & Logistics, the ship’s operator, advised the ATSB that gaps and holes in the tween decks would in future be fully covered by fire resistant tape prior to hot work, in addition to other measures such as using fire blankets, to protect areas below hot work.
The other six fires
In addition to this occurrence and the three previous fires above investigated by the ATSB, there have been six other similar fires involving Briese ships since 2007. The cause of each of the fires was attributed to welding, cutting or gouging work related to the cargo securing arrangements. These six fires involved the following ships.
BBC Barbarossa, 2007
BBC Everest, Campana (Argentina), 2013
BBC Fuji Baltimore (USA), 2014
BBC Bangkok, Rostock (Germany), 2014
BBC Seine Onslow (Australia), 2014
Jan, Tanjung (Malaysia), 2017
While the severity of each fire varied, such incidents have commonly resulted in significant economic impact. For example, Briese reported that the 2007 fire on BBC Barbarossa resulted in almost EUR 8,000,000 worth of claims relating to firefighting efforts, waste disposal and cargo damage. More significantly, as reported by Hong Kong’s Administration, this type of fire incident has previously resulted in fatalities.[8]
Company response to previous fires
In response to these previous fires, Briese issued numerous fleetwide communications, including fleet circulars and safety bulletins. The communications often described the fires and identified their causes as a failure of crew or contractors to observe basic shipboard procedures and controls for hot work.
The company used these communications to reinforce the SMS requirements for conducting hot work on deck, such as adhering to the risk assessment and work permit procedures, conducting proper inspections prior to work and, maintaining a fire watch at all times. For example, a fleet circular issued on 28 July 2010 recommended the use of fire-retardant blankets for stopping sparks from falling through gaps in the tween deck and for covering fire prone cargo.
On 25 March 2021, while discharging cargo in Port Hedland, a fire broke out in BBC Rhonetal’s number two hold. Immediate efforts by the ship’s crew to control the fire with fire hoses were not successful so the cargo hold was closed and flooded with carbon dioxide using the ship’s fixed fire-extinguishing system.
The fire was extinguished several days later with the assistance of shore emergency services. The fire caused significant damage to some cargo in the hold, but damage to the ship was restricted to localised paint damage. No one was seriously injured.
Origin
Shortly before smoke was observed rising from the lower hold, the bosun had been cutting fastenings with a plasma torch in an area on the tween deck which was located above a vibrating screen assembly stowed in the lower hold. The screen was later identified by firefighters from the Western Australia Department of Fire and Emergency Services as the origin of the fire.
The fire started when sparks and globules of molten metal generated by the plasma cutting fell through gaps in the tween deck and down onto the screen below. The hot material swiftly melted through the protective plastic covering on the screen and then onto its combustible internal components, which ignited shortly afterwards.
Fire watch
The shipboard safety management system (SMS) provided guidance for performing hot work safely. It required fire watches to be in place at all times during the work, including in adjacent compartments where appropriate, and fire rounds to be made for at least 2 hours following the conclusion of hot work.
However, the recall and reassignment of the ordinary seaman (OS) on fire watch to other duties meant that there was no fire watch in the lower hold while the bosun continued hot work activity above. At the time the OS was recalled, there was no sign of fire or smoke in the lower hold. This indicates that the fire almost certainly developed after the OS was recalled and left his post.
Had a continuous fire watch been maintained, it is likely that the sparks and molten metal falling from above would have been immediately identified and smothered by the OS before they ignited the combustible cargo. In the unlikely event that they did catch fire, the OS would have been stationed to promptly raise the alarm and attempt extinguishing the fire with the firefighting equipment at hand.
Fire risk assessment
Hot work practices on board indicated some general awareness of the fire risk associated with removing sea fastenings. This was evidenced by the completion of a hot work permit, availability and deployment of firefighting and fire prevention equipment and assigning a fire watch.
However, no efforts were made to assess or address specific fire risks associated with the flammability of vibrating screens in the lower hold. As a result, the cargo was not protected with specific, effective measures such as fire-retardant coverings and a continuous fire watch.
Safety management system implementation
During the 15 years preceding the fire on BBC Rhonetal, there had been nine similar fires on Briese ships. The ATSB investigated three of those fires and found that in each occurrence, fundamental risk controls such as maintaining a continuous fire watch and protecting combustible cargo from the hot work with suitable fire-retardant coverings were not followed.
In response to the previous fires, the company had undertaken action to improve relevant SMS processes and disseminate various fleet circulars highlighting the inherent dangers of hot work and the associated risk controls. As such, BBC Rhonetal’s SMS, consisting of dedicated procedures for hot work and associated tools such as work permit and risk assessment forms, in addition to relevant fleetwide circulars, should have provided sufficient guidance for the safe removal of sea fastenings.
However, factors that contributed to those earlier fires, such as inadequate risk assessment, not maintaining a continuous fire watch and not protecting combustible cargo with fire retardant coverings, also contributed to the fire on BBC Rhonetal.
The evidence shows that this fire resulted because the SMS procedure and guidance were not properly followed. A proper inspection for fire risks at the work site and surrounding areas was not undertaken. The risk assessment procedure was not followed to ensure specific risks associated with the task were identified, documented and mitigated and a continuous fire watch was not maintained for the duration of the hot work. While a safety meeting was held for the planned hot work, it was not effectively executed so as to prepare the crew for carrying out the task safely.
Non-adherence to basic safety precautions and hot work procedures have been a common factor in fires on board Briese ships. The number and frequency of these incidents in recent years, together with the circumstances of this fire, shows that the company had not effectively implemented its SMS procedures across its fleet.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the fire within cargo hold number two on board BBC Rhonetal, Port Hedland, Western Australia on 25 March 2021.
Contributing factors
Sparks and molten metal generated from the removal of sea fastenings from the tween deck using a plasma cutting torch fell through gaps in the deck and ignited combustible cargo stowed in the cargo hold below.
Hot work continued on the tween deck after the fire watch had been asked to leave the lower hold to perform other duties. As a result, no one was in a position to immediately identify and respond to the fire that developed in the lower hold.
Other factors that increased risk
Items of cargo stowed in the lower hold below the work site were not adequately assessed as a fire risk and protected before starting the hot work.
BBC Rhonetal’s managers had not effectively implemented the shipboard safety management system procedures in place to prevent the fire. This was the tenth such fire on a company ship in the past 14 years, and the fourth investigated by the ATSB, identifying similar contributing factors. [Safety issue]
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the marine industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety Management System implementation
Safety issue number: MO-2021-002-SI-01 Safety issue description: BBC Rhonetal’s managers had not effectively implemented the shipboard safety management system procedures in place to prevent the fire. This was the tenth such fire on a company ship in the past 14 years, and the fourth investigated by the ATSB, identifying similar contributing factors.
Glossary
AMSA
Australian Maritime Safety Authority
AWST
Australian Western Standard Time
BBC
Briese Bischoff Company
CCTV
Closed-circuit television
CO2
Carbon dioxide
COSWP
United Kingdom Code of Safe Working Practices for Merchant Seafarers
DFES
Western Australia Department of Fire and Emergency Services
DNV GL
Det Norske Veritas, Germanischer Lloyd
EUR
Euro (European Monetary Unit)
IMO
International Maritime Organisation
ISM Code
International Safety Management Code
MCA
United Kingdom Maritime and Coastguard Agency
MSIN
Merchant Shipping Information Note (Hong Kong)
OS
Ordinary Seaman
PPA
Pilbara Ports Authority
SAR
Hong Kong Special Administrative Region
SMS
Safety Management System
SWL
Safe Working Load
UTC
Coordinated Universal Time
VHF
Very High Frequency
VTS
Vessel Traffic Services
WA
Western Australia
Sources and submissions
Sources of information
The sources of information during the investigation included the:
directly involved officers and crew of BBC Rhonetal
Briese Schiffahrts
Briese Heavylift
BBC Chartering and Logistics
Western Australia Department of Fire and Emergency Services
Australian Maritime Safety Authority
Pilbara Ports Authority
Flag administration of Antigua and Barbuda.
References
International Maritime Organization (IMO) 1995, International Management Code for the Safe Operation of Ships and for Pollution Prevention (ISM Code) as amended, IMO, London.
Maritime and Coastguard Agency (MCA), Code of Safe Working Practices for Merchant Seafarers, 2015.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
directly involved officers and crew of BBC Rhonetal
Briese Schiffahrts
Briese Heavylift
BBC Chartering and Logistics
Western Australia Department of Fire and Emergency Services
Australian Maritime Safety Authority (AMSA)
Pilbara Ports Authority
The Department of Marine Services and Merchant Shipping for the ship’s flag State (Antigua and Barbuda) administration.
Submission were received from:
Briese Schiffahrts and Briese Heavylift
AMSA
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 8 March 2021, the crew of a Piper PA-28 aircraft, registered VH-PZG, were conducting a dual training flight from Bankstown Airport to the Bankstown training area, New South Wales.
At the top of climb, at about 4,000 ft near Warragamba Dam, the instructor detected a faint exhaust gas smell and recalled feeling a little more tired than when they took off and mildly lightheaded. The instructor then looked up at the carbon monoxide detector and observed a localised discolouration (indicating the likely presence of carbon monoxide in the cabin).
The instructor opened all fresh air vents and windows, and ensured the heater was off. They then advised the student of the positive indication and decided to return to Bankstown. The student continued to fly the aircraft back while the instructor monitored the situation and detector.
The aircraft landed safely at Bankstown and the crew were taken to hospital for medical examination.
What the ATSB found
The ATSB found that the disposable carbon monoxide detector had indicated elevated levels of carbon monoxide in the cabin during the flight. Positive carbon monoxide indications were also reported in two previous flights nine months prior. However, subsequent post-incident inspections and test flights were unable to replicate the conditions nor determine the source of the carbon monoxide.
Safety message
Carbon monoxide (CO) is a colourless and odourless gas, and its presence may not be detected until the development of physical symptoms and/or cognitive effects. Therefore, operators and owners of piston-engine aircraft are strongly encouraged to install a CO detector with an active warning to alert pilots to the presence of elevated levels of CO in the cabin. Should any smell or sensation of illness develop, pilots should check their CO detector, ensure cabin heat has been turned off, open all fresh air vents and windows, make prompt decisions to land as soon as possible, and use all available resources for assistance. Further information on CO poisoning and detectors can be found at the following:
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 8 March 2021, the crew of a Piper PA-28 aircraft, registered VH-PZG, were conducting a dual training flight from Bankstown Airport to the Bankstown training area, New South Wales. The student was sitting in the left-hand seat and the instructor in the right.
At about 0800 Eastern Daylight-saving Time,[1] the crew started the engine and taxied the aircraft to the run-up bay to carry out engine run-ups,[2] with the side window open, the fresh air vents closed and the heater off. Prior to take-off, the crew closed the side window, and switched the windscreen demister and carburettor heat off. No indication of carbon monoxide (CO) was observed on the disposable CO chemical spot detector while the aircraft was on the ground. At about 0815 the aircraft departed from Bankstown heading to the training area.
During climb, between 1,500 ft and 2,000 ft, the instructor noticed warm air coming from the right floor air vent. Soon after, at the top of climb, at about 4,000 ft near Warragamba Dam, the instructor detected a faint exhaust gas smell and recalled feeling a little more tired than when they took off and mildly lightheaded. The instructor then looked up at the CO detector card, that was located on the ceiling above their head, and observed a localised discolouration (Figure 1 left).
The instructor opened all fresh air vents, windows and ensured the heater was off. The instructor then advised the student of the positive indication and they both agreed to return to Bankstown. The instructor considered diverting to Camden Airport, which was closer, but they felt that their impairment was mild and could safely operate the aircraft to Bankstown. The student continued to fly the aircraft back while the instructor monitored the situation and the detector. The student recalled initially feeling normal, however, halfway back to Bankstown recalled feeling a little lightheaded and had a dry warm taste in their mouth that lasted a few of hours.
At 0845, the aircraft landed safely at Bankstown. The crew were subsequently taken to hospital for a medical examination. Both crew members reported feeling better after breathing fresh air for about half an hour before they left for the hospital.
Figure 1: Discoloured carbon dioxide detector during different stages of the flight
Source: Instructor
Context
Medical information
General health and fitness
Both crew members were well rested and felt fine on the day of the incident. They were non-smokers and did not have any pre-existing medical conditions that could have contributed to the incident.
Carboxyhaemoglobin
Blood samples were taken about an hour after the aircraft had landed at Bankstown. The results of the tests indicated a carboxyhaemoglobin (COHb) level of 1.4 per cent for the instructor and 1 per cent for the student. Neither crew members were administered oxygen.
Carbon monoxide is an odourless, colourless and tasteless gas formed by the incomplete combustion of carbon-containing materials. When inhaled, it preferentially binds to haemoglobin, the oxygen carrying molecule in red blood cells. This creates COHb compounds and prevents oxygen from binding to the molecule and being transported, resulting in oxygen starvation.
Recent ATSB investigations AO-2020-026 and AO-2017-118 have shown that normal endogenous levels of COHb are generally reported to fall within the range of 0.4-0.7 per cent. Smokers, and those living in an urban area, may have higher than average levels of COHb that fall within 1-6 per cent. Carbon monoxide has a half-life of 4-5 hours at sea level, meaning the COHb will reduce to half its initial value within that time, after the source of CO has been removed. The CO half-life can be reduced to 80 minutes with the administration of pure oxygen.
The physical symptoms and cognitive effects of CO poisoning can worsen with an increasing level of COHb, however, different individuals’ reactions to a given COHb level can vary (Lacefield et al., 1982). Researchers have found that a person’s ability to perform complex tasks can be adversely affected at levels of 10 per cent or less (Baselt, 2014). It has also been found that the effects of CO can begin to show with the deterioration of psychomotor function at COHb levels of about 3 per cent (Hawkins, 1993).
Many studies have stated that an individual should not experience physical symptoms below 10 per cent. Such studies reference very similar tables that illustrate a specific COHb level and their associated symptoms, starting from 10 per cent up to 60-80 per cent. However, Hampson et al. (2012) discovered that the widely used tables were unreliable and, though they may differ slightly, come from a 1920’s publication and are based on the symptoms experienced by three men who, between them, reached maximum COHb levels of up to 28 per cent during a total of 10 low level CO exposures.
In addition to this, various studies have found that the clinical symptoms presented by a patient can be inconsistent with their recorded COHb levels (Hampson & Hauff, 2007; Hampson et al., 2012; Widdop, 2002; Oliverio & Varlet, 2018). Curry (1972, as cited in Widdop, 2002) also found that in some forensic investigations, where the evidence strongly pointed to CO poisoning, the blood analysis indicated only low to normal COHb levels.
Post-incident aircraft inspection
After the incident, and prior to any maintenance activity, engineers conducted engine ground runs with a digital CO detector and were unable to detect CO leaking into the cabin. The engineers then inspected the aircraft and did not find any faults in the exhaust system or the heater and demister ducting.
A non-standard (improvised) gasket had been used between the cabin heat distributor box and firewall. The gasket material did not have any odour associated with it and appeared to have been in place for some time. The current maintainer could not find any record of when the gasket was installed. Due to the lack of smell, the ATSB determined that the material was unlikely to be the CO source.
The flapper valve for the heater system was also found to be out of adjustment and would not fully close. The ATSB contacted Piper Aircraft to determine if CO could leak into the cabin via the valve. They advised fresh air enters the engine compartment via the nose cowling and is vented to the heater muff through a flexible hose located on the baffling at the rear of the engine. The air is then heated and vented into the cabin area through a valve, which is controlled from the instrument panel. When the valve is completely closed off, the heated air is vented back into the engine compartment. As a result, the effect of an out of adjustment valve would act like partial heat was on. However, unless a fault was found within the exhaust system, it was unlikely that CO could leak into the cabin via the flapper valve.
Several weeks after the inspection, the operator took the aircraft for a test flight along with a digital detector. The highest concentration of CO obtained was 25 parts per million (ppm) during taxi (with the side window and door ajar) and take-off (with all windows and doors secured), while in cruise the highest indication was 3 ppm.
The maximum exposure level, as recommended by Safe Work Australia, is 30 ppm over an 8-hour period.
Previous carbon monoxide incidents
VH-PZG was the subject of two other reported CO events in the year before this incident on 12 June and 9 July 2020. In the first incident (which involved the same instructor, but a different student), a discolouration on the detector was observed by the instructor at the runway holding point. The instructor reported feeling lightheaded, had a headache and poor cognition, the student was unsure whether they were experiencing any symptoms. The training flight was aborted, and the aircraft was returned to the apron. The instructor reported they were taken to hospital and the blood analysis indicated the instructor’s COHb level was 0 per cent and the student’s was 1.8 per cent, noting that the student was a smoker.
In the second incident, a discoloration on the detector was observed by the crew after the engine rpm was increased to 2,000 for engine run-ups. The run-ups were aborted, and the aircraft was taxied back to the apron. Neither the instructor nor the student reported experiencing any symptoms and were not taken to hospital.
Two days before the second incident the CO card detector was replaced with a new one. Both post-incident inspections were unable to determine the source of the CO. The exhaust and heater systems were inspected, and no faults were found. Engine ground runs and test flights were conducted with a digital CO detector and no indication of CO was detected.
Carbon monoxide detector
The aircraft was fitted with an Aviation Supplies and Academics disposable CO chemical spot detector, attached to the ceiling just above the right seat. The detector was 8 months old and within the manufacturer’s 12-month replacement period. It consisted of an orange‑coloured circle (spot) in the middle of the card, which was designed to change colour to grey/black following a chemical reaction with CO in the immediate vicinity. The spot then returns to normal (orange) after it has been exposed to fresh air (Figure 1, bottom). The chemical reaction depends on the concentration of CO in the air and the time of exposure. This detector was designed to react to a minimum of 50 ppm of CO within 30 minutes, 100 ppm within 10 minutes and 200 ppm within 4 minutes.
A study conducted by the United States Federal Aviation Administration (FAA) (Hossein et al., 2009) noted the useful life range of these types of detectors are between 30-60 days. The manufacturer’s website advises the detector will last up to 12 months, however, they also recommend the detectors are replaced with a new one every 3-6 months depending on the environment they are being used in.
An additional limitation of this type of detector is that it does not actively alert the pilot to the presence of CO. Therefore, its effectiveness relies on the pilot regularly monitoring the detector throughout the flight. It is also dependent on the detector being easily visible and accessible, in a well-lit environment. In a low ambient light environment, the discolouration of the chemical spot, from orange to a grey/black colour, can be difficult to see.
Safety analysis
Elevated levels of carbon monoxide
The crew reported observing a discoloration of the carbon monoxide (CO) detector and experienced very mild symptoms and cognitive effects. While it was possible for CO card detectors to give an unreliable indication, the same aircraft was involved in two other incidents, nine months prior, and the detector was replaced with a new one two days before the second incident. In addition, the crew’s blood tests after this incident indicated mildly elevated carboxyhaemoglobin levels, which in conjunction with the card indication, was consistent with CO in the cabin.
Despite the above, the post-incident aircraft ground runs and subsequent flight tests were unable to detect elevated levels of CO in the aircraft cabin. While the inspection revealed a non-standard gasket and an out of adjustment flapper valve, the ATSB determined them both to be unlikely sources of CO due to the lack of smell from the foreign material and the absence of observed defects in the exhaust system. As a result, the source of the leak was not determined.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the positive carbon monoxide indication involving a Piper PA-28, registered VH-PZG that occurred near Bankstown Airport, New South Wales on 8 March 2021.
Other factors that increased risk
The crew were exposed to elevated levels of carbon monoxide in the aircraft cabin.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
flight crew
aircraft operator
maintenance organisation for VH-PZG.
References
Baselt, R.C. (2014). Disposition of Toxic Drugs and Chemicals in Man (10th ed.). Seal Beach: Biomedical Publications.
Hampson, N.B., Dunn, S.L., & Members of the UHMS/CDC CO Poisoning Surveillance Group. (2012). Symptoms of carbon monoxide poisoning do not correlate with the initial carboxyhemoglobin level. Journal of theUndersea & Hyperbaric Medical Society, 39(2): 657-665. PMID:22530449
Hampson, N.B., & Hauff, N.M. (2008). Carboxyhemoglobin levels in carbon monoxide poisoning: do they correlate with the clinical picture? American Journal of Emergency Medicine, 26(6): 665-669. https://doi.org/10.1016/j.ajem.2007.10.005
Hawkins, F. H. (1993). Human Factors in Flight (2nd ed.). Aldershot, England: Ashgate Publishing.
Hossein Cheraghi, S., Jorgensen, J., & Myose, R.Y. (2009). Detection and prevention of carbon monoxide exposure in general aviation aircraft (DOT/FAA/AR-09/49). Federal Aviation Administration. http://www.tc.faa.gov/its/worldpac/techrpt/ar0949.pdf
Oliverio, S., & Varlet, V. (2019). Total blood carbon monoxide: Alternative to carboxyhemoglobin as biological marker for carbon monoxide poisoning determination. Journal of Analytical Toxicology, 43(2): 79-87. https://doi.org/10.1093/jat/bky084
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
flight crew
aircraft operator
maintenance organisation for VH-PZG.
No submissions were received from the directly involved parties.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 4 March 2021, the crew of a Leonardo Helicopters AW139, registered VH-PVO and operated by the Victoria Police Air Wing, were re-assigned from an aerial search near Coldstream to a search and rescue task in Orbost, Victoria. Due to the cloud conditions, the pilot upgraded the flight from visual to instrument flight rules. While en route to Bairnsdale at their cruising altitude of 5,000 ft, the helicopter entered cloud and shortly after the enhanced ground proximity warning system activated with the alert ‘caution terrain’. The pilot initiated a climbing left turn to avoid Mount Baw Baw, which had a maximum elevation of 5,138 ft.
What the ATSB found
The ATSB found that, while en route to Bairnsdale below the lowest safe altitude, the helicopter entered cloud in the vicinity of Mount Baw Baw, which resulted in activation of a ground proximity alert. The pilot identified the location of the terrain threat and conducted a climbing turn away.
The helicopter was below the lowest safe altitude as the pilot had incorrectly assessed the in-flight conditions as visual meteorological conditions after the helicopter reached 5,000 ft in the vicinity of Coldstream (based on their estimate of height above the cloud tops). As a result, the pilot elected to remain at 5,000 ft instead of recalculating the lowest safe altitude as the flight progressed.
The ATSB also found that the operator did not have a procedure for pilots when upgrading from visual to instrument flight rules in-flight. This would reduce the likelihood of an error when replanning in-flight, which was reported to be an infrequent task and higher-than-normal workload task, particularly in single-pilot operations.
What has been done as a result
After the incident, Victoria Police Air Wing developed an instrument flight rules upgrade procedure for inclusion in their operations manual. This procedure includes the acceptable methods for calculating lowest safe altitude and was circulated to all their pilots.
Safety message
This investigation highlighted the importance of lowest safe altitude calculations and to recalculate the lowest safe altitude appropriate for the area of operations.
Operators should also review their operations manual to ensure they have procedures in place to adequately capture their operating procedures in order to minimise the likelihood of decision‑making errors.
The occurrence
On 4 March 2021, at about 1120 Eastern Daylight-saving Time,[1] the crew of a Leonardo Helicopters AW139, registered VH-PVO and operated by the Victoria Police Air Wing, were tasked with a search and rescue in Orbost, Victoria. At the time of the tasking, they were assisting with an aerial search near Coldstream. On board was the pilot and two tactical flight officers.
After receiving the new task, the crew discussed whether there was sufficient fuel onboard to continue to Orbost without returning to their base at Essendon Airport. They decided that they could proceed with the re-tasking without returning to Essendon, but would have to refuel at Bairnsdale Airport, before commencing the task at Orbost. Due to the presence of cloud to the east, in the direction of Bairnsdale, the pilot decided to upgrade the flight from visual[2] to instrument flight rules[3] and contacted air traffic control (ATC) accordingly.
Part of the upgrade to instrument flight rules required the pilot to calculate the lowest safe altitude[4] (LSALT) for the flight. At the time of the upgrade, the helicopter was about 17 NM (31 km) to the north‑north-east of Moorabbin Airport. Therefore, the pilot initially calculated the LSALT of 5,000 ft above mean sea level (AMSL) based on the Moorabbin 25 NM (46 km) minimum sector altitude of 4,700 ft, with the intent to revise en route. The pilot knew they were within the 25 NM minimum sector altitude at the time as they were familiar with the area from previous training exercises. Once this was calculated and a clearance was received from ATC, the pilot set 5,000 ft as the target altitude in the autopilot altitude acquire function.
The helicopter’s forward-looking infrared camera footage recorded the helicopter entering cloud at about 2,800 ft and emerge on top of the cloud at about 4,475 ft (Figure 1), before leveling off at 5,000 ft. At interview, the pilot recalled the helicopter entered cloud at about 2,700 ft and emerged at 3,500–4,000 ft. The pilot turned the volume down on the intercom radios to focus on the other tasks associated with the upgrade, including filing a flight plan with Airservices Australia. The pilot also entered the flight path from Coldstream to Bairnsdale into OzRunways[5] and noted they would be flying through the East Sale restricted airspace[6] to reach Bairnsdale (Figure 2). The pilot was cognisant of the need to obtain an airways clearance for the East Sale restricted airspace early in the flight.
Figure 1: Camera footage exiting cloud at 4,475 ft on climb to 5,000 ft
Source: Victoria Police Air Wing
Figure 2: Exemplar flight plan showing the route from Coldstream to Bairnsdale
Source: The pilot, using OzRunways, annotated by the ATSB
Several minutes later, the pilot conducted the cruise checks while at 109 kt indicated airspeed[7] and recalled that they were below LSALT as they were now outside the Moorabbin minimum sector altitude. Further, they were below the published grid LSALTs[8] of 6,400 ft and 7,300 ft on their track to Bairnsdale (Figure 2). However, the pilot assessed that they were about 1,000 ft above a layer of cloud and that the conditions were day visual meteorological conditions,[9] which was an acceptable reason to operate below LSALT.[10] Based on this, the pilot decided to continue the flight at 5,000 ft and advised ATC accordingly (Figure 3).
Figure 3: Camera footage at cruising altitude above cloud at 4,998 ft
Source: Victoria Police Air Wing
The pilot turned up the intercom radio volume to communicate with the tactical flight officers about the police tasking and plan for the day. To assist the pilot, the tactical flight officer in the front-left seat entered the radio frequency for East Sale. At about 1139, the pilot made several attempts to contact the East Sale air traffic controller but was unsuccessful. The tactical flight officer checked the frequency in the En Route Supplement Australia[11] and confirmed it was correct. Shortly after, the pilot observed the cloud tops beginning to rise while trying to verify the East Sale radio frequency, but initially believed they would pass just over the cloud tops. However, as shown on the camera footage, the helicopter entered the cloud just below the tops while the pilot was continuing to attempt to contact East Sale (Figure 4).
Figure 4: Camera footage of the rising cloud near Mount Baw Baw just prior to the ground proximity alert
Source: Victoria Police Air Wing
Upon entering the cloud, the helicopter’s enhanced ground proximity warning system (EGPWS) alert for ‘caution terrain’ activated. In response, the pilot checked the primary flight display, which depicted ‘green hash’ terrain right of track (indicating the location of the terrain hazard). Therefore, the pilot initiated a climbing left turn to the north to avoid the terrain, which was Mount Baw Baw with a maximum elevation of 5,138 ft. Shortly after commencing the climbing turn, a second ‘caution terrain’ alert activated, and the pilot continued the climbing left turn. The helicopter exited the cloud to the north of Mount Baw Baw and the camera footage revealed the sky was clear to the east. The pilot contacted ATC to request a climb to 6,000 ft and the flight continued without further incident. Figure 5 depicts the flight path with the location of Mount Baw Baw and the EGPWS alerts.
Figure 5: Map showing VH-PVO’s flight path with key locations
The pilot held an Air Transport Pilot’s Licence (Helicopter), multi-engine helicopter instrument rating, a type rating for the AW139, and Class 1 Aviation Medical Certificate. At the time of the incident, the pilot had accumulated 5,094 hours of aeronautical experience, of which 144 hours were on the AW139. The pilot had completed an instrument proficiency check in October 2020 and had recorded 5.8 hours of instrument flight in the previous 90 days, including five instrument approaches.
The pilot reported being well rested on the day of the incident. A review of the sleep and roster information obtained found there was a low likelihood the pilot was experiencing a level of fatigue known to have an adverse effect on performance.
Radar altimeter setting
As part of the ‘after-start’ checklist, the radar altimeter (RADALT)[12] low height warning bug was required to be set to 400 ft. Around the time of the incident, there were known interference issues between the downlink from the camera and the RADALT, which could produce spurious low height RADALT indications. The pilot did not recall any spurious indications or recall referring to the RADALT during the incident flight. They also reported the low height warning bug was likely set to 400 ft as per the after-start checklist.
Recorded information
The helicopter was fitted with an enhanced ground proximity warning system (EGPWS), which would activate when terrain or obstacles were detected about 26 +/-5 seconds ahead of the helicopter. The ‘caution terrain’ alert indicated the helicopter had entered the ‘soft’ threshold for the terrain awareness mode (a ‘warning terrain’ alert would indicate the ‘hard’ threshold). The ‘green’ display reported by the pilot indicated terrain was at least 250 ft below the helicopter’s altitude.[13] According to the helicopter’s flight manual, if a caution alert occurred in-flight, the pilot should ‘verify the aircraft flight path and correct as necessary’.
The ATSB analysed the information from the flight data recorder. Key events included:
at 1140:11, the EGPWS alert ‘caution terrain’ activated when the aircraft was at 5,000 ft above mean sea level (AMSL) and 131 kt indicated airspeed
at 1140:13, a pitch up and left roll were initiated after the alert
at 1140:43 the EGPWS alert ‘caution terrain’ activated again when the aircraft was at 5,150 ft AMSL and 75 kt indicated airspeed.
at 1140:45 a pitch up and left roll were initiated again immediately after the second alert.
At the time of the first alert, the helicopter was about 1.8 NM (3.3 km) horizontally and 200 ft above terrain. At the time of the second alert, the helicopter was within 0.8 NM (1.5 km) horizontally and 350 ft above terrain. Figure 6 depicts the flight path with terrain contours and the relative positions of the EGPWS alerts.
Figure 6: Topographic map of flight path showing time of the alerts and altitudes
Source: Google Earth and flight data recorder, annotated by the ATSB
Meteorological conditions
The Bureau of Meteorology forecast conditions for the area around Mount Baw Baw for the time of the incident were for broken clouds between 1,000 ft and 3,000 ft. Footage from the forward‑looking infrared camera on the helicopter showed that the cloud base was about 2,800 ft and the cloud tops were about 4,500 ft near Coldstream. On approach to Mount Baw Baw, the helicopter entered cloud at about 5,000 ft, which was just below the cloud tops based on the camera footage. The footage also indicated the sky was clear immediately to the east of Mount Baw Baw.
A briefing occurred at the Victoria Police Air Wing each morning, which included the weather. The pilot recalled discussing the weather at that morning’s briefing and that it was ‘average’ [clouds present] inside the Melbourne basin, but clear outside the basin. In this situation, the pilot reported their standard brief would be, ‘weather is a bit average in the basin this morning…but outside the basin it’s pretty much green [clear] everywhere so we can go anywhere outside the basin, but we might have to fly IFR [instrument flight rules]’. The pilot recalled that the forecast freezing level was above 10,000 ft on the day of the incident and therefore did not expect icing to be a factor if an IFR flight was required.
Visual meteorological conditions
For the sector from Coldstream to Bairnsdale, the helicopter started in Class C (controlled airspace) before leaving Class C and entering Class G airspace (outside controlled airspace). The following criteria apply to visual meteorological conditions (VMC) below 10,000 ft in Class C and Class G airspace:
5,000 m visibility
1,000 ft vertical separation from cloud
1,500 m lateral separation from cloud.
In addition, if operating in Class G airspace at or below 3,000 ft above mean sea level or 1,000 ft above ground level, whichever is highest, the minimum flight visibility was 5,000 m, remaining clear of cloud and in sight of ground or water.
Calculating lowest safe altitude under instrument flight rules
Introduction
The Victoria Police Air Wing operations manual stated that obstacle/terrain avoidance below the lowest safe altitude (LSALT) or minimum sector altitude (MSA) is a pilot responsibility unless using an air traffic services assigned level, in accordance with air traffic surveillance service terrain clearance procedures. Further, responsibility returns to the pilot when the aircraft is being flown in visual meteorological conditions.
The operations manual also outlined that minimum altitudes for IFR operations shall be from one of three methods, in accordance with Aeronautical Information Publication (AIP):
pilot calculated
IFR charts (terminal area chart/en route chart)
departure and approach procedures for minimum sector altitudes and/or instrument approach landing procedures.
The AIP also stated that an aircraft must not be flown under the IFR, lower than the published lowest safe altitude or the pilot calculated lowest safe altitude, unless permitted by Civil Aviation Regulation 178 or otherwise approved by the Civil Aviation Safety Authority.
Civil Aviation Regulation 178: Minimum height for flight under I.F.R., stated that an aircraft cannot be flown below the lowest safe altitude calculated in accordance with published procedures except in accordance with subregulation (4). Subregulation (4)(d) permitted an aircraft to be flown below the lowest safe altitude if it was being flown by day in visual meteorological conditions.
Minimum sector altitude
The AIP stated that MSA was the lowest altitude that provided a minimum clearance of 1,000 ft above all objects located in an area contained within a sector of a circle of 25 NM (46 km) or 10 NM (19 km) radius centred on a significant point, the aerodrome reference point, or the heliport reference point. Moorabbin Airport had a 10 NM MSA of 3,700 ft and a 25 NM MSA in the north-east sector of 4,700 ft. As the helicopter was about 17 NM (31 km) to the north-north-east of Moorabbin Airport, the pilot requested clearance to climb to 5,000 ft as the initial cruise altitude with the intent to revise later when established on track to Bairnsdale.
Grid lowest safe altitude
The grid lowest safe altitude is the lowest safe altitude shown for a grid on an IFR chart (terminal area chart/en route chart). The AIP stated that a pilot using a grid LSALT for obstacle clearance is responsible for determining the allowance for navigation error that should be applied, considering the limitations of the navigation aids or method of navigation being used for position fixing. This navigation error allowance must be applied to the proposed track. The highest grid lowest safe altitude falling within the area covered by the determined navigation error must be used.
When the pilot loaded the flight plan into OzRunways, they were not in the vicinity of a published IFR route for the flight to Bairnsdale, so the pilot had the option to compute a pilot calculated LSALT or to use the published grid lowest safe altitude (Figure 2). The flight plan from Coldstream to Bairnsdale was across three lowest safe grid altitudes, which were 6,400 ft, 7,300 ft and 7,000 ft, with respect to the direction of travel. Therefore, the LSALT required for the route was 7,300 ft.
Instrument flight rules traffic travelling east were required to use the odd thousands of feet for their cruising levels. If the grid LSALT of 7,300 ft was selected, the flight required a cruising level of 9,000 ft to Bairnsdale to remain above LSALT and comply with the IFR cruising levels. The infrared camera footage indicated the sky was almost certainly clear at this level and icing would not have been a risk.
Pilot calculated lowest safe altitude
When the pilot upgraded the flight to IFR, air traffic control (ATC) was advised that the selected cruising level was based on the pilot calculated method for LSALT. The AIP stated that, if a route or route segment was not shown on an AIP aeronautical chart, the lowest safe altitude can be calculated by the pilot. Based on the area to be considered for RNP 2 navigation,[14] this must be within an area of 5 NM (9 km) surrounding and including the departure point, the destination and each side of the nominal track.
Furthermore, if the highest obstacle is more than 360 ft above the height determined for terrain, the LSALT must be 1,000 ft above the highest obstacle. Otherwise, 1,360 ft must be added to the highest terrain and the LSALT rounded up to the nearest 100 ft.
This required a pilot calculated LSALT of 6,500 ft from Coldstream to Bairnsdale, to account for the peak of Mount Baw Baw at 5,138 ft, which would have permitted a cruising level of 7,000 ft in accordance with the IFR cruising levels.
Instrument flight rules upgrade in-flight
Upgrading to IFR in-flight was a relatively infrequent task. The pilot reported that it happened about once every few months. The chief pilot estimated they upgraded once or twice a year, whereas other pilots were unable to provide a frequency. The nature of Victoria Police Air Wing operations required their helicopters to conduct taskings predominantly under visual flight rules in sight of ground or water. However, the nature of the weather and terrain across Victoria required them to have the capability to transit between tasks using IFR procedures over high terrain. Prior to the incident, Victoria Police Air Wing did not have a published procedure for upgrading to IFR in-flight. The tasks involved in an upgrade to IFR would include:
calculating the LSALT based on an applicable method
reviewing the freezing level and risk of icing
entering the LSALT and the destination in the navigation system
contacting and filing a flight plan with air traffic control
determine a method to climb to LSALT that ensures terrain clearance.
Regarding the last item, when an aircraft departs IFR from an airport, or conducts a missed approach from an instrument approach procedure, it is the compliance with the respective procedure that provides terrain clearance assurance until the aircraft reaches LSALT. Therefore, in the case of an IFR upgrade in-flight, the pilot must determine a suitable method to provide terrain clearance assurance until reaching LSALT.
Related occurrences
A review of the ATSB database found a recent similar occurrence of a helicopter entering instrument meteorological conditions while flying below LSALT.
ATSB occurrence 202002989
On 12 June 2020, a Bell 412 conducting aerial work departed Jandakot Airport, Western Australia under visual flight rules. During climb, the crew requested an upgrade to IFR and a clearance to the south-east. The crew entered cloud at 1,000 ft, which was below the minimum sector altitude of 2,500 ft. The controller issued a safety alert and cleared the helicopter to climb to 4,000 ft.
On the morning of 4 March 2021, the crew of a Leonardo Helicopters AW139, registered VH-PVO and operated by the Victoria Police Air Wing, received a ground proximity alert for ‘caution terrain’ while en route from Coldstream to Bairnsdale. As a result, the pilot initiated a climbing left turn to avoid terrain and the helicopter exited the cloud.
The analysis will discuss the calculation of the lowest safe altitude (LSALT), upgrading from visual to instrument flight rules in flight, and related procedures.
Flight into cloud below lowest safe altitude
While en route from Coldstream to Bairnsdale, the helicopter was operating at an altitude of 5,000 ft and was initially above the cloud tops. The peak of Mount Baw Baw, with an elevation of 5,138 ft, was located close to the planned track but was obscured by the formation of orographic uplift cloud for the flight path from west to east. As the required pilot calculated LSALT was 6,500 ft and the grid LSALT was 7,300 ft, the flight at 5,000 ft was below both the LSALTs available for this route. While they recognised the cloud tops were rising, the pilot initially believed the helicopter would clear the tops. This likely resulted in the pilot continuing along track, rather than requesting either a climb or diversion left/right of track, which resulted in the helicopter entering the cloud below LSALT. Almost immediately after entering cloud, the EGPWS alert ‘caution terrain’ activated. In response, the pilot identified the terrain and initiated a climbing left turn.
Assessment of in-flight conditions
As part of the instrument flight rules upgrade, the pilot was required to calculate a LSALT. The pilot used their current location and the 25 NM (46 km) Moorabbin Airport minimum sector altitude of 4,700 ft as the reason for selecting 5,000 ft. The pilot indicated this LSALT was sufficient at the time, with the intent to revise it later in-flight.
After establishing the helicopter in the cruise at 5,000 ft, the pilot completed the cruise checks, which included an altitude check. At the time, the pilot assessed the cloud tops were between 3,500 ft to 4,000 ft. Therefore, at 5,000 ft, the pilot perceived that they were about 1,000 ft above the cloud tops. Visual meteorological conditions require 1,000 ft vertical separation from cloud, which was consistent with the pilot’s assessment of the conditions at the time. Therefore, the pilot assessed that the conditions complied with the regulations permitting instrument flight below the LSALT. Based on this, the pilot decided to continue at 5,000 ft. However, recorded data from the forward-looking infrared camera indicated that the cloud tops were about 4,500 ft in the vicinity of Coldstream, and therefore the helicopter was not operating in visual meteorological conditions, which would have required the pilot to recalculate a LSALT. Therefore, the flight continued below LSALT as a result of the pilot incorrectly assessing the conditions.
IFR upgrade procedure
Although all pilots in the Victoria Police Air Wing maintain instrument ratings, the majority of the flights were operated under visual flight rules for tasking purposes. The incident pilot reported that they did not frequently upgrade from visual to instrument flight rules but needed to be prepared to do so if required by the conditions and tasking. The procedural requirements for an in-flight upgrade would therefore need to be recalled from memory while maintaining sufficient attentional resources on the task of flying and navigating the helicopter in a single-pilot environment. This results in an environment of concurrent task demands, with separate tasks competing for the pilot’s limited resources, which can increase the likelihood of a loss of awareness of the environment.
The purpose of a procedure is to provide the best way to operate the aircraft safely and efficiently by outlining the steps required to be completed at a point in time. This is a rules-based process to accomplish a task, which reduces the need to problem-solve. While the operator did not have an upgrade procedure at the time of the incident, such a procedure would incorporate both regulatory operating requirements and aircraft systems operating requirements. Therefore, a single dedicated procedure could improve the efficiency of recall, thereby reducing the cognitive task demands and likelihood of an error.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the Flight below lowest safe altitude involving Leonardo Helicopters AW139, VH-PVO, 44 km north-north-west of Latrobe Regional Airport, Victoria, on 4 March 2021.
Contributing factors
While en route to Bairnsdale below lowest safe altitude, the helicopter entered cloud in the vicinity of Mount Baw Baw, which resulted in activation of a ground proximity alert. The pilot identified the location of the terrain threat and conducted a climbing turn away.
The pilot incorrectly assessed the in-flight conditions as visual meteorological conditions after the helicopter reached 5,000 ft in the vicinity of Coldstream and elected to remain at this altitude instead of recalculating the lowest safe altitude.
Other factors that increased risk
The operator did not have a procedure for pilots when upgrading from visual to instrument flight rules in-flight. This would reduce the likelihood of an error when replanning in-flight, which is a higher-than-normal workload task.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Additional safety action by Victoria Police Air Wing
As a result of the incident, Victoria Police Air Wing have developed an instrument flight rules upgrade procedure to be incorporated into their operations manual. This procedure was circulated to all their pilots and included the acceptable methods for calculating lowest safe altitude and the requirement to ensure terrain clearance while on climb to that altitude.
Glossary
AGL Above ground level
AMSL Above mean sea level
AIP Aeronautical Information Publication
ATC Air traffic control
CASA Civil Aviation Safety Authority
EGPWS Enhanced ground proximity warning system
IFR Instrument flight rules
MSA/LSALT Minimum sector altitude (MSA) and lowest safe altitude (LSALT)
RADALT Radar altimeter
VFR Visual flight rules
VMC Visual meteorological conditions
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot
front and rear tactical flight officers onboard the flight
Victoria Police Air Wing
Bureau of Meteorology
Airservices Australia
Department of Defence
Civil Aviation Safety Authority.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
The pilot, front and rear tactical flight officers, Victoria Police Air Wing, Airservices Australia, and the Civil Aviation Safety Authority.
Submissions were received from:
The pilot, front and rear tactical flight officers, and Victoria Police Air Wing.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Occurrence summary
Investigation number
AO-2021-010
Occurrence date
04/03/2021
Location
44 km north-north-west of Latrobe Valley Airport
State
Victoria
Report release date
02/12/2021
Report status
Final
Investigation level
Defined
Investigation type
Occurrence Investigation
Investigation status
Completed
Mode of transport
Aviation
Aviation occurrence category
Flight below minimum altitude
Occurrence class
Serious Incident
Highest injury level
None
Aircraft details
Manufacturer
Leonardo Helicopters
Model
AW 139
Registration
VH-PVO
Serial number
31878
Aircraft operator
Starflight Victoria PTY LTD contracted to Victoria Police Air Wing
On the morning of 20 February 2021, a Robinson R22 Beta helicopter, registered VH-HCX, was being repositioned from a storage depot near Geraldton Airport to Murchison House Station near Kalbarri, Western Australia. Shortly after lifting off, at about 30–40 ft above the ground, the engine’s performance reduced and the helicopter began to descend. The pilot completed a forced running landing in a yard adjacent to the point of departure. The pilot then elected to reposition the helicopter. However, on becoming airborne, the helicopter began to rotate nose‑right. In response the pilot landed the helicopter.
What the ATSB found
The ATSB found that an inlet valve in the engine’s number-four cylinder sustained thermal damage, which led to reduced engine performance and required the pilot to conduct a forced landing. The loss of directional control during the subsequent lift-off resulted from a loss of drive to the tail rotor due to the tail rotor drive shaft fracturing in torsional overstress close to its connection with the tail rotor gearbox.
Safety message
This occurrence serves as a reminder for pilots of piston engine helicopters, like the R22, to be alert for unexpected yawing and transient reduced engine performance during flight. These characteristics may be symptomatic of developing engine intake valve damage. If this condition remains unattended it can lead to an increased risk of induction backfire events, and significant loss of engine power.
Additionally, when a loss of engine power or abnormal operation is encountered, an appropriately licensed maintenance engineer should complete an engine cylinder inspection in accordance with the helicopter and engine manufacturer’s most recent service instructions before further flight. Maintenance organisations should note that when completing a differential compression test of the engine cylinders, an accompanying borescope inspection of the cylinders and valves will provide an effective method to visually assess the condition of these components.
The investigation
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 20 February 2021, a Fortescue Helicopters‑operated, Robinson R22 Beta, registered VH-HCX, was to be repositioned from a storage depot near Geraldton Airport, to Murchison House Station, near Kalbarri Western Australia. Once at the station, the helicopter was to be utilised for aerial goat mustering.
At about 0830 Western Standard Time,[1] the pilot arrived to prepare the helicopter for flight. The pre-flight check was completed with no anomalies identified. The pilot reported that prior to departure the engine was started and allowed to warm-up. The helicopter was then maintained in a low hover, a few feet above the ground, for about 30 seconds. With no abnormalities detected, the pilot transitioned the helicopter to forward flight and commenced climbing away.
At approximately 30–40 ft above the ground, the pilot detected increased vibration and described the engine sound changing to like a ‘chaff cutter.’ The engine then emitted a loud backfire and the helicopter yawed[2] ‘savagely’ nose-left an estimated 40–45°. The pilot reported a significant reduction in engine power and the helicopter started to descend. A bystander at the depot, who was watching the departure, observed a plume of smoke behind the helicopter.
Aware that a forced landing was imminent, the pilot prepared to conduct a running landing onto a yard adjacent the departure point. The helicopter landed heavily, in a slightly nose high attitude, resulting in the skids rocking in a heel-toe manner several times along the gravel surface before coming to a stop in line with the helicopter’s flight path (Figure 1).
The pilot remained in the helicopter with the engine and rotor system running and completed several checks to determine the serviceability of the engine. The pilot identified that the rough engine running had eased. With no further engine issues evident the pilot elected to reposition the helicopter. Upon lifting off the pilot identified an uncommanded right yaw and a loss of anti-torque response from the tail rotor foot pedals. In response, with the helicopter having yawed through about 150°, the pilot landed and shutdown the engine.
Figure 1: VH-HCX at the landing site
Several heel-toe skid marks were created during the landing. The helicopter subsequently yawed right after the pilot attempted to reposition the helicopter.
Source: Fortescue Helicopters
Context
Helicopter damage
The pilot examined the helicopter after landing and identified that the tail rotor drive shaft had fractured at its connection to the tail rotor gearbox (Figure 2). The helicopter was grounded, and the operator contracted a maintenance organisation that specialised in Robinson helicopters to complete an engineering examination and damage assessment.
In their report, the maintenance organisation noted that the tail rotor gearbox was correctly installed and free to rotate with no internal damage. All hardware that attached the tail rotor drive shaft, rear flex plate, and tail rotor gearbox input coupling was in place and in the manufacturer’s specified assembly order. The tail rotor blades were inspected and found serviceable with no evidence of foreign object damage to their surfaces. There were no indications that the tail section had contacted the ground. Although assessed as non-contributory to the shaft fracture, the maintenance organisation also reported that the friction from a bolt within the tail rotor drive shaft damper assembly was found to be less than manufacturer’s specification. Excluding the fractured shaft, no significant defects were identified with the tail rotor drive line components.
Figure 2: Tail rotor drive shaft fracture and schematic of the general area of the fracture
Source: Fortescue Helicopters, Robinson Helicopter Company, annotated by ATSB
During the post-occurrence inspection of the engine, maintenance engineers identified that the number-four cylinder was unable to hold pressure when subjected to a compression check. That cylinder was removed and, on further inspection, localised thermal damage to the inlet valve was identified (Figure 3). Reduced cylinder compression and valve damage can lead to engine power reduction, induction backfires, and aircraft yawing. No further defects were identified with the helicopter.
Figure 3: Internal view showing localised heat damage to the inlet valve from the number‑four cylinder of the engine
Source: Azimuth Aviation, annoted by the ATSB
ATSB technical examination
Partial disassembly and examination of the helicopter’s tail rotor gearbox and the fractured tail rotor drive shaft was completed at the ATSB’s technical facilities in Canberra. No anomalies with the gearbox bevel gears and bearings that could have overloaded the drive shaft were identified. A runout check confirmed the drive shaft to be straight.
The fracture surfaces of the drive shaft were examined at high magnifications using both an optical and scanning electron microscope (SEM). The optical examination confirmed that the shaft fracture was located close to the welded flange with the entire section of shaft twisted and its cross-section inwardly necked in a ductile manner (Figure 4). The SEM examination confirmed the presence of gross ductile overstress features. There were no pre-existing defects identified from manufacture, or operational damage such surface scoring, fatigue cracking, denting or corrosion that might have otherwise weakened the shaft and predisposed it to fracture.
Figure 4: Gross ductile twisting and overstress fracture of the drive shaft
Source: ATSB
Operational and maintenance history
The helicopter was manufactured in the United States in 1991 and first registered in Australia in the same year. It was fitted with a Lycoming O-320-B2C four-cylinder reciprocating piston engine. The airframe had accumulated 9,700 hours total time in service. The helicopter had last been overhauled in December 2018 and had since accrued 1,484.2 hours in service to the occurrence flight. The tail rotor drive shaft was replaced with a new item at the overhaul in 2018.[3]
The operator advised the ATSB that in August 2020, approximately 320 hours prior to the occurrence flight, one tail rotor blade had sustained a dent to the leading edge that required replacement of the rotor blade assembly. The tail rotor drive shaft was inspected at that time and all shaft runout measurements were found to be within the manufacturer’s limits.
The operator further reported that in December 2020 the engine had been running roughly due to a fouled spark plug in the number-four cylinder. Additionally, in the few weeks prior to the occurrence, the helicopter had been flown in the Geraldton area, and during that time the engine had exhibited periods of reduced engine performance and associated momentary uncommanded yawing. On the day of the occurrence, the pilot had elected to conduct the precautionary 30‑second hover due to uncertainty associated with the previous period of intermittent engine performance.
Manufacturer’s advice
The helicopter manufacturer advised that the VH-HCX tail rotor drive shaft fracture was highly consistent with a slowing (extreme drag) or sudden stoppage of the tail rotor blades and that in certain instances, contact with a foreign object such as water, tall grass, plastic bags or small birds may not result in visible damage to the blades.
The ATSB sought further advice from the helicopter manufacturer as to whether the fracture could have resulted from the helicopter being operated at a resonant engine/shaft speed. They noted that it would require an extended operational period at a resonant speed for the shaft to become damaged. Resonant shaft vibrations of concern exist at engine speeds of 15 per cent (below engine idle speed), 60 percent and 132 per cent (above red line). The manufacturer advised that a tail rotor drive shaft will permanently bend and fracture if operated at the higher resonant speed. The damper bearing will dampen the resonance at the two lower speeds.
The manufacturer also indicated that there has been no recorded instance within their R22 fleet of damage to the tail rotor drive shaft due to a rough running engine.
Other occurrences
Cylinder head inlet valve distress
In 2018, prompted by increasing industry reports of engine issues involving Robinson R22 and R44 helicopters, the Civil Aviation Safety Authority issued an Airworthiness Bulletin (AWB) 85-025 Robinson R22/R44 Engine Intake Valve and Valve Seat Distress, which examined in detail many of the factors that may contribute to cylinder head intake valve damage. The AWB noted that intake valve wear, the formation of solid oil deposits (coke) on the valve stem, and valve leakage can be avoided by:
not exceeding the cylinder head upper temperature limit (red line) of 500 °F (260 °C) during operation
minimising the duration of extended ground operations in high-temperature ambient conditions
ensuring adequate engine cool down prior to shut down in accordance with the manufacturer’s recommendations. The R22 Pilot’s Operating Handbook noted that:
If ambient temperatures are greater than 38 °C, an extended cool down is recommended. Operate at cool down RPM for at least 1 minute before reducing to idle.
CASA advised that a failure to comply with these recommendations may result in an induction backfire, engine power loss and airframe yaw. In a severe event this could lead to a loss of engine power. The following maintenance recommendation was provided:
The LAME should listen for the sound of leakage at each intake valve while performing a differential compression test in accordance with the latest revision of Lycoming SI No. 1191. A cylinder borescope inspection should also be performed.
Tail rotor drive shaft fracture
A search of the Australian, Canadian and United States Federal Government aviation service difficulty reporting databases[4] identified only one other[5] similar reported instance of a Robinson R22 tail rotor drive shaft fracture event. The defect report noted that the failure occurred during take-off and that the helicopter may have sustained an overspeed or had been operated within a resonant speed range.
Safety analysis
Engine power loss
Shortly after the Robinson R22 departed from the Geraldton storage depot, the helicopter sustained an engine power loss that required the pilot to conduct a forced landing. The investigation of this occurrence identified that the power loss was due to thermal damage to an inlet valve from the number-four engine cylinder.
The clearance created by in-service thermal damage to the valve head reduced the inlet valve sealing capacity. This, in turn, likely permitted combustion gases to bypass the valve seat and extend back through the intake of the engine producing the reported backfire, power loss and associated airframe yaw. The previous instances of yawing and reduced engine performance while the helicopter was operated in the Geraldton region provided an indicator of the developing inlet valve damage.
Furthermore, the damage to the valve and its associated effects on engine performance was consistent with the information contained within the industry advice produced by the Civil Aviation Safety Authority.
Tail rotor drive shaft
The ATSB examination identified that the drive shaft fractured in overstress from torsional loading that led to total separation of the shaft from its connection to the rear flex plate and tail rotor gearbox. It was while attempting to reposition the helicopter following the forced landing that the pilot was unable to maintain directional control of the helicopter due to the complete loss of anti‑torque thrust from the tail rotor system. The ground contact marks created by the helicopter skids during the forced landing were relatively straight, which indicated that the drive shaft was probably intact at the time of ground contact.
The ATSB was unable to conclusively determine the reasons for the driveshaft fracture, which probably occurred during the running landing. The surfaces around the drive shaft fracture contained no evidence of pre-existing damage, mechanical rubbing or rotational contact damage. There was no evidence that the engine was operated at a resonant speed nor was there damage identified to the tail rotor blades from contact with a foreign object that could have overstressed the shaft. The previous damage to one of the rotor blades was considered unlikely to have been contributory as the shaft had been inspected following that occurrence and found to be serviceable.
A search of several databases revealed limited previous instances of similar failures in R22 helicopters. Additionally, the manufacturer reported no instances of tail rotor drive shaft fracture due to a rough running engine.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the engine failure and forced landing of a Robinson R22 Beta helicopter that occurred 4 km south‑west of Geraldton Airport on 20 February 2021.
Contributing factors
The inlet valve from the number-four cylinder of the engine sustained thermal damage, which led to reduced engine performance during the occurrence flight and the requirement for the pilot to perform a forced landing.
During subsequent repositioning, the pilot was unable to maintain directional control of the helicopter due to the tail rotor drive shaft fracturing in torsional overstress close to its connection with the tail rotor gearbox.
Sources and submissions
Sources of information
The sources of information during the investigation included:
Fortescue Helicopters
the pilot of VH-HCX
Heli-Flight
Azimuth Aviation
Robinson Helicopter Company
Civil Aviation Safety Authority
Lycoming Engines
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
Fortescue Helicopters
the pilot of VH-HCX
Heli-Flight
Azimuth Aviation
Robinson Helicopter Company
Civil Aviation Safety Authority
Lycoming Engines
Submissions were received from:
Heli-Flight
Azimuth Aviation
Robinson Helicopter Company
Civil Aviation Safety Authority
Lycoming Engines
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the afternoon of 26 February 2021, a Queensland Rail suburban express passenger train was approaching the Kianawah Road level crossing in the Brisbane suburb of Wynnum West, Queensland. The boom barriers were in the lowered position and other protection devices (flashing lights) were active at the level crossing.
At the same time, after stopping to give way to opposing road traffic at the intersection, immediately adjacent to the level crossing, a motor vehicle turned towards the crossing. It then continued through the level crossing, bypassing the lowered boom barrier, colliding with the train. The motor vehicle was destroyed, and the sole occupant was fatally injured. The only 2 occupants of the train, the driver and guard, were not injured.
What the ATSB found
The ATSB found that there was a 3.1 m gap between the tip of the boom barrier and the median island, which meant that the barrier only partially blocked road traffic that approached the level crossing from Lindum Road. In this instance, it was very likely that the driver of the motor vehicle followed the turn line markings on the road surface, which directed them past the end of the lowered boom barrier onto the level crossing and into the path of the approaching train. Safety concerns raised by local road users and work undertaken by the Government also indicated that the road-rail interface at the Kianawah Road level crossing was complex and visually noisy from a road user’s perspective.
Queensland Rail had not been managing risk at level crossings in accordance with the requirements of its level crossing safety standard. In particular, the standard stated that public and pedestrian level crossings were to be assessed every 5 years or sooner. However, the Kianawah Road level crossing had not been assessed for 19 years. Some other level crossings with high instances of incidents and accidents had also not been assessed for 20 years.
It was also identified that, between 2016 and 2021, Queensland Rail had just one person qualified to assess all their public, pedestrian, private, maintenance, and construction level crossings, which numbered in the thousands. Of the 1,138 public level crossings that required assessment within the 5-year timeframe, just 52 were completed.
Further, Queensland Rail and the Brisbane City Council did not have a formal road-rail interface agreement in place at the time of the accident, although negotiations were ongoing. This was a missed opportunity to collectively identify any unique risks associated with the level crossing and manage and maintain those risks through an agreed process.
What has been done as a result
Following the accident at the Kianawah Road level crossing, Queensland Rail and the Brisbane City Council have formalised an interface agreement encompassing all level crossings where they have a shared responsibility. In addition, Queensland Rail:
Has installed a new boom barrier at the level crossing, compliant with the Australian Standard (1742.7), that fully protects road users when approaching the active crossing from Lindum Road. In addition, rectified a safety issue where the boom barrier did not fully comply with the requirements of the Australian Standard at 29 other level crossings within its jurisdiction.
Assessed the Kianawah Road level crossing in accordance with the Australian Level Crossing Assessment Model (ALCAM) to establish a current assessment risk score rating.
Has trained 4 internal staff to undertake ALCAM assessments and introduced a procurement process to engage a contract firm to update outstanding regional ALCAM assessments over the next 5 years.
Safety message
Level crossings are a complex environment and are well known for their high-risk consequences. While the ultimate preference is to avoid or remove level crossings, this is often very costly and not a practical solution. Therefore, it is important that road authorities and rail infrastructure managers collectively manage these risks. To achieve this, they should enter into an interface agreement as soon as possible to identify and manage hazards and risks at the road and rail interface, so far as is reasonably practicable.
Further, it is also important that organisations ensure they follow the requirements of their safety management system, as it sets the minimum safety standard to ensure the effective management of risk.
The occurrence
Events prior to the collision
On 26 February 2021, a Queensland Rail suburban express passenger train, designation E820, was being operated as a scheduled service between Roma Street and Cleveland, in Brisbane, Queensland.
About the same time, the driver of a small red motor vehicle was visiting an address in the Brisbane suburb of Hemmant. At about 1330 local time, they left that address to drive to the neighbouring suburb of Wynnum.
As the driver of the motor vehicle travelled along Lindum Road, in an easterly direction, they approached the intersection of Lindum Road and North Road, which was located on the northern side of the Kianawah Road level crossing. As illustrated in Figure 1, the likely intention of the driver was to turn right at the intersection and pass though the level crossing enroute to Wynnum. A friend reported to the Queensland Police Service they did not know if the vehicle driver had been through this intersection previously, but assumed they would have been using a navigation system to assist with directions.
Figure 1: Road user’s likely intended route from Lindum Road through the level crossing
Source: Google Earth, annotated by the ATSB
Closed-circuit television footage from Lindum Station showed the motor vehicle approach the Lindum Road – North Road intersection and stopped in a queue behind 3 other road vehicles. During a pause in traffic, the first of the 3 vehicles turned right and could be seen passing through the level crossing.
At that time, the train approached the level crossing from the west, on the ‘Up’[1] Cleveland line, with only a driver and guard on board. The universal traffic control[2] replay showed that the train activated the Kianawah Road level crossing automatic protection system at 1339:17, when it was 820 m from the crossing. The train’s event recorder showed it was travelling at about 94 km/h at the time.
As the second vehicle in the queue moved away and passed through the level crossing, the flashing lights were active. As the third vehicle in the queue passed through the level crossing, the boom barriers at the crossing were lowering. Simultaneously, the driver of the small red motor vehicle moved forward and stopped at the intersection stop line. They delayed at the stop line to give way to a vehicle that was approaching from the north along North Road. That vehicle turned across the front of the motor vehicle into Lindum Road. After it passed, witnesses stated, and the station footage showed that the driver of the motor vehicle momentarily moved forward but came to a stop as another road vehicle (a utility vehicle) approached the intersection from North Road.
The event recorder showed that the train driver sounded the country horn[3] at the whistle board[4] to warn of the train’s approach to the level crossing. The speed of the train was 94 km/h, and the train’s headlights, visibility lights, and marker lights were illuminated.
At 1339:37, the universal traffic control replay and station footage showed that the boom barriers of the level crossing had fully lowered. The driver of the motor vehicle remained stationary at the stop line of the intersection waiting for the utility vehicle to pass on North Road. At that point, the train was about 280 m from the level crossing.
The driver of the utility stated that their intention was to turn right at the intersection (North Road – Lindum Road) into Lindum Road. As they approached the intersection, they noticed that the boom barrier at the level crossing was down (horizontal) and saw a train approaching the level crossing. As they turned right in front of the small red motor vehicle, they observed the driver looking left and right as if they were ready to move forward after they had passed. After turning into Lindum Road, the driver of the utility looked through the rear-view mirrors and observed the small red motor vehicle move off and approach the level crossing.
The accident
At 1339:44, the front of train camera showed that the small red motor vehicle was on the correct side of the road (to the left of the median island in direction of travel) as it entered the level crossing and passed to the right of the lowered boom barrier. At that time, the train was about 60 m from the level crossing and travelling at 94 km/h.
In interview, the train driver stated the vehicle was on the correct side of the road as it entered the crossing from their left (train’s direction of travel). The driver indicated that the vehicle was travelling at a slow and consistent speed as it passed through the crossing, and the driver of the motor vehicle was looking straight ahead.[5] On sighting the vehicle, the train driver applied emergency braking and sounded the town horn.
At 1339:47, the front left side of the train collided with the motor vehicle at about 82 km/h. The train continued a further 280 m before coming to a stop. The sole occupant of the motor vehicle was fatally injured. The driver and guard were not injured, and the train sustained minor damage.
Context
Train information
Queensland Rail (QR) service E820 was an electric suburban train scheduled to run express from Roma Street Station to Cleveland Station. The service was worked by new generation rollingstock 769, and the driver was operating from driving cab 8769 at the time of the accident. The train consisted of 6 cars, with a length of 146.7 m and a weight of 260 t.
For visibility purposes, the front of the new generation rollingstock (leading cab) were fitted with light emitting diode headlights, white marker lights, and visibility lights that flashed alternately for 20 seconds when either the town or country horn was operated. At the time of the accident all visibility lighting on the front of the train was illuminated.
The train was equipped with a front of train camera and an event recorder, which contained closed-circuit television images and data relevant to the accident journey. There were no faults or defects recorded with the operation of the train, and at the time of the accident the braking system functioned as designed.
Train crew information
The driver was qualified to operate all classes of QR electric passenger trains, including the new generation rollingstock, and was route competent to operate within the Brisbane suburban rail network, which included the Cleveland corridor.
The event recorder showed that the driver operated the train in accordance with QR’s operational guidelines on approach to the Kianawah Road level crossing and followed post-accident protocols immediately after the accident.
The driver and guard of train service E820 were drug and alcohol tested after the accident and both returned 0.00% readings.
Road vehicle driver information
The driver of the motor vehicle held a current Queensland driver’s licence. The licence was subject to a condition, which required the driver to wear corrective lenses while driving. A friend of the driver, who was the last contact prior to the accident, advised the Queensland Police Service that the driver of the vehicle would have been wearing either glasses or contact lenses as they never drove without them.
The police advised that there were no prescription glasses found at the accident site and the forensic report indicated that there was no evidence of the driver wearing contact lenses. The police further stated that due to the high impact collision and debris at the scene, it was possible that the driver’s glasses or contact lenses (if worn) were dislodged and overlooked when processing the accident site.
A toxicology report provided by the Queensland Health Forensic and Scientific Services indicated that the driver of the motor vehicle involved in the accident was not affected by alcohol or drugs.
An examination of the driver’s mobile phone records showed that there was no call or short message service (SMS) activity around the time of the accident or immediately before.
Meteorological information
The weather at the time of the accident was fine and clear. The driver of E820 recalled it being a fine, clear, sunny day as they approached the Kianawah Road level crossing.
At about 1340, the sun was high in the sky (azimuth: 331.61°and elevation: 69.02°). Therefore, sun glare had negligible effect on the motor vehicle driver’s approach to the intersection of Lindum and North Roads or the warning devices (half boom barriers and flashing lights) at the level crossing.
Rail and road information
Cleveland railway corridor
The Cleveland railway corridor was a branch line that extended from Park Road Station, an inner‑city station, east through to Cleveland Station. There were 8 public level crossings on the corridor. The railway corridor catered mainly for electric suburban passenger trains although there was a third line (dual gauge line) specifically for freight trains, which branched off from the railway corridor at Lindum.
On a normal weekday there were more than 150 train services that traversed the railway corridor, most of them suburban trains. The maximum speed for suburban trains on the corridor was 100 km/h and 80 km/h for freight trains.
Accident location
The accident occurred at the Kianawah Road level crossing in the suburb of Wynnum West, which was located 17 km east of the Brisbane central business district or 14.1 rail km from Park Road. The area surrounding the level crossing was a mix of light industrial and low‑medium density residential development. In near proximity to the level crossing was Lindum Station, Iona College (with a complement of 1,700 students), and a retirement village and aged care facility (Figure 2). The suburb had a population of about 16,000.
Brisbane City Council (BCC) controlled and maintained the road network, which included a multi‑modal intersection on either side of the level crossing where the Cleveland passenger and Port of Brisbane freight rail lines separated the local road network. The rail corridor was controlled and maintained by QR.
Figure 2: Density of population surrounding the Kianawah Road level crossing
Source: Google Earth, annotated by the ATSB
Road and rail interface
North Road and Kianawah Road ran along a north-south axis that formed a continuous road that spanned the northern and southern side of the Kianawah Road level crossing. The roads intersected the rail corridor at a 45° angle. There was one traffic lane in each direction and a painted median island separated the 2-way traffic lanes that passed through the level crossing.
Immediately prior to the level crossing, there were 2 intersections, one on either side of the crossing. On the northern side, Lindum Road connected with North Road and on the southern side, Sibley Road connected with Kianawah Road (Figure 3).
The North Road approach to the level crossing had a stop line painted on the road pavement just prior to the North Road – Lindum Road intersection. The stop line only applied to road users when the level crossing protection devices were active. There was also a turn-right only traffic lane from North Road that connected with Lindum Road just prior to the level crossing.
Lindum Road divided into 2 lanes at the intersection. The left lane was for road traffic turning left into North Road away from the level crossing. The right lane was for traffic turning right and passing through the crossing onto Kianawah Road. At the Lindum Road – North Road intersection there was a stop sign with a related stop line relevant to Lindum Road. From the stop line, turn line markings painted on the road pavement guided road traffic towards the entrance of the level crossing at about a 40o angle. If the level crossing was active, road users in the right lane were required to remain at the stop line until the level crossing and opposing road traffic were clear.
Depicted in Figure 3 are the potential variations in road vehicle travel through the level crossing (yellow). The path of the motor vehicle involved in the accident (orange), the direction of the train’s travel, and the point of the collision are also shown.
Figure 3: Kianawah Road level crossing showing intersections and general traffic flow
Source: Google Earth, annotated by the ATSB
Reported safety concerns
Over many years, members of the public have raised safety concerns about the Kianawah Road level crossing and its adjoining multi-modal intersections with the 3 levels of government.
In 2019, the Queensland Department of Transport and Main Roads undertook a review of 65 level crossings in south east Queensland to assist with developing a framework for prioritising upgrades. The review of each crossing considered the imperative for change, safety, network efficiency, and accessibility and connectivity. The Lindum Station level crossing was found to have less vehicles, buses, cyclists, and pedestrians than the average level crossing, along with a similar boom gate downtime. However, the crossing had more near misses and boom gate strikes than the average level crossing, likely indicating a heightened safety risk.
Consequently, in 2019-2020, the Queensland Government (Department of Transport and Main Roads), with support of the Australian Government, undertook a study to determine how to best enhance safety, network efficiency and accessibility to improve the Lindum Station precinct.
The study included a community engagement program (online engagement portal and a face‑to‑face component) allowing interested parties to provide feedback to enhance safety in the precinct for the local community and road users. One of the key topics raised, which was recorded in the subsequent report, was safety concerns relating to the level crossing and the complexities of the adjacent intersections. The report stated that:
As many as 50 per cent of respondents have had a safety-related incident at the Lindum [Kianawah Road] level crossing and 58 per cent currently avoid using the level crossing due to safety concerns or congestion issues.
Information provided by the Department of Transport and Main Roads, relating to the level crossing and the adjacent intersections, stated:
Safety
• The level crossing has a significant history of safety occurrences, including a recent pedestrian fatality in February 2019, and a high number of boom [barrier] strikes and near misses over the previous decade
• The intersections adjacent to the level crossing are complex and difficult to navigate for motorists, cyclists and pedestrians
- Driver confusion and frustration is likely contributing to increased risk taking by motorists, particularly for right turns, with a high [road accident] crash rate over the last five years, including three hospitalisations and the majority with failing to give way violations.
Traffic efficiency
• Currently the level crossing is closed between 28% and 36% of the time during peak periods, dropping to less than 20% in the inter-peak and off-peak periods
• Vehicles approaching from Lindum Road are experiencing a one-minute delay on average during the morning and afternoon peak periods and can experience queues of over 100 metres in the morning peak period and 200 metres in the afternoon peak period.
The study investigated a number of short-term, medium-term, and long-term options for addressing the issues identified at the Lindum Station precinct. These ranged from upgrading and the signalisation of intersections adjacent to the level crossing, constructing an active transport bridge over the rail corridor, to providing a grade separated road over the rail.
Following the 2019-20 study, the Department of Transport and Main Roads, in conjunction with Brisbane City Council, Queensland Rail and the Australian Government Department of Infrastructure, Transport, Regional Development, Communications and the Arts commenced a jointly funded preliminary business case investigation into long-term options for the level crossing precinct including the viability of a future grade separated road overpass.
Brisbane City Council and Queensland Rail were also working with the Department of Transport and Main Roads to develop a new upgraded level crossing alignment with traffic signalisation to further improve safety. The project was jointly funded by all 3 levels of government and at the time of publication of this investigation report, it was currently in the design phase.
Reported occurrences
According to QR data, there have been numerous reported incidents at the Kianawah Road level crossing involving road vehicles passing through the crossing after the protection had activated. More specifically, during the 2-year period from March 2019 to February 2021, there were:
5 reports by train drivers of applying emergency braking due to a road vehicle passing through the crossing with the boom barriers down
5 reports where a boom barrier had been hit by a road vehicle
6 reports where a boom barrier had come down on top of a vehicle
14 reports of a road vehicle passing through the crossing while the boom barrier was already down
9 reports of a road vehicle passing through the crossing while the boom barrier was coming down
5 reports of multiple vehicles passing through the crossing while the boom barrier was coming down
9 reports of multiple vehicles passing through the crossing while the lights were flashing.
Given the nature of the reports involving multiple vehicles, it was likely that the number of vehicles passing through the crossing after the lights were activated and/or the boom barrier started descending was much higher than reported. There was insufficient detail in most reports to determine how many events were associated with vehicles entering the crossing from Lindum Road.
In the same period, there were also numerous reports of pedestrians passing through the pedestrian gates at the crossing when they were closed.
Additional data supplied by QR recorded that since December 2015, the Kianawah Road level crossing had the fifth highest collision/near miss occurrences of level crossings in south-east Queensland (Table 1).
Table 1: South-east Queensland level crossings collision/near miss information since December 2015
Ranking
Level crossing
Collision/near miss numbers
1
Old Beaudesert Road
26
2
Oates Avenue
19
3
Beenleigh Road
16
4
Nathan Road
16
5
Kianawah Road
15
Level crossing information
General information
The National Level Crossing Safety Strategy 2023-2032 (National Level Crossing Safety Committee, 2023) emphasised that level crossing occurrences result in a significant social and economic impact on individuals, communities, and business. While total avoidance or removal of level crossings is the ultimate preference, both these options are often very costly and not practical. The strategy noted the complexity of the road-rail interface:
The nature of level crossings as an interface between road and rail transport is a complex environment so creating change to improve level crossing safety is a shared responsibility. While capital investment is part of the ongoing solution, strategic national collaboration is also at the forefront of actions.
The Office of the National Rail Safety Regulator stated in its Rail Safety Report2021‑2022:
There are more than 20,000 level crossings in Australia and at all of them there exists a level of risk to safety – indeed, other than suicide and trespass, accidents at level crossings are the primary cause of railway related fatalities among the general public.
There were 38 level crossing collisions between a passenger or freight train and road vehicle reported in the 2021–2022 financial year, resulting in three fatalities and three serious injuries:
» two of the fatalities were road vehicle occupants and one was a cyclist;
» all three of the serious injuries were road vehicle occupants; and
» 66% of the collisions occurred at crossings protected by active controls, such as lights and boom gates, representing an increase of 56% from 2020–2021.
Level crossing traffic control devices
Flashing signal assembly
According to the Australian Standard (AS) 1742.7, (Manual of uniform traffic control devices Part 7: Railway crossings), the railway crossing flashing signal assembly (RX-5) shall be used at crossings that require flashing signal control. The assembly consisted of an R6-25 sign, W7-2-2 sign, R6-9 sign and a railway crossing flashing signal that consisted of twin red circle aspects arranged horizontally and equipped to flash alternately. They may also include provision of multiple flashing signals to cover all approaches and may be supplemented by boom barriers (Figure 4).
An inspection of the northern side of the Kianawah level crossing identified an RX-5 assembly was installed for approaching road traffic from both North Road and Lindum Road. The flashing signal of the RX-5 assembly was designed to flash automatically on the approach of a train. Post‑accident functionality testing and an on-site observation conducted by QR, which included the warning devices at the level crossing, identified the flashing signals of the assembly were operating correctly.
Figure 4: Railway crossing flashing signal assembly (RX-5)
Source: Standards Australia
Boom barriers
Regarding the installation of boom barriers at level crossings, AS 1742.7 stated:
Boom barriers shall comprise as a minimum, a boom extending from the left side of the roadway-
(a) to the right hand kerb or edge of a one-way roadway;
(b) to the edge of a median island; or
(c) in the case of a two-way roadway, to the dividing line or centre of the roadway if no line is marked.
The boom in its lowered state should be placed at right angles to the road centre-line.
The active protection at the Kianawah Road level crossing was supplemented by half boom barriers. Under normal operating conditions, the boom barriers activated automatically when the signalling system detected an approaching train. The red lamps fitted to the boom barriers were equipped with light emitting diodes.
The boom barrier on the northern side of the level crossing, measured 9.94 m. In its lowered state it fully spanned the entire width of North Road. However, the boom barrier only partially protected road traffic from entering the crossing from Lindum Road as it did not extend to the edge of the median island in accordance with AS 1742.7. As a result, a 3.1 m gap existed between the tip of the boom barrier and the painted median island (Figure 6). To understand the relevance of the 3.1 m gap, it is necessary to provide comparisons to appreciate the significance. The width of:
a general traffic lane in an urban environment was 3.0–3.5 m[6]
the road vehicle involved in the accident was about 1.8 m.
Information provided by QR identified 29 other locations within its jurisdiction where the boom barrier of a level crossing did not comply with the requirements of AS 1742.7. In particular, the requirements of (b) and (c) above.
The boom barriers and their associated lamps had a design cycle time of 28 seconds prior to the arrival of a train at the crossing. The time and sequence order was:
8 seconds - lamp activation
10 seconds - boom barriers to lower
10 seconds - boom barriers in the horizontal position before the train’s arrival.
A post-accident functionality test of the track circuitry and the activation of the boom barriers determined they operated as designed and within the requirements of AS 1742.7. In addition, all light voltages at the lamp terminals associated with the level crossing and boom barriers were assessed and found to be within tolerance levels.
Road signage
A BCC signs and pavement marking plan, relevant to roads approaching the Kianawah level crossing, showed an RX-7 assembly (Figure 5) was required on the left side of the roadway on approach to the Lindum Road – North Road intersection. The AS 1742.7 stated:
An RX-7 assembly [combined W7-4 and W8-3(R) or W8-3(L) signs] shall be used to give advance warning on a through road of a crossing which is controlled by flashing signals when the crossing:
(a) is on a side road; and
(b) is too close to the intersection to provide the appropriate distance required for erection of the W7-4 sign on the side road …
The assembly shall be positioned on the through road on the left side of each approach to the intersection.
For a side road on the right the W8-3(R) sign shall be used.
An inspection of road signage, conducted by QR on 3 March 2021, identified an RX-7 assembly on the left side of Lindum Road about 80 m from the intersection, however, the W8-3 sign was missing from the assembly. It could not be determined if the W8-3 signal was in place at the time of the accident.
Figure 5: Railway crossing flashing signals ahead on side road assembly (RX-7)
Source: Standards Australia
Stop lines
Regarding the requirement for stop lines, AS 1742.7 stated:
At all railway crossings on sealed roads controlled by RX-2, RX-5, and RX-6 (STOP sign, flashing signals and gate control) assemblies, a stop line shall be provided on each approach to indicate the location at which vehicles must stop as and when required by law. It shall be placed at right angles to the road centre-line as follows:
(a) At STOP signs - 3.5 m minimum back from the nearest rail at its closest point.
(b) At flashing signal control - 3 m minimum back from the signal pedestal or boom barrier in its lowered position.
(c) At gates - 3 m minimum back from the gates when closed to road traffic.
In the absence of a dividing line or median, the stop line shall extend only to the centre of the seal.
A site inspection identified the stop line markings on the road pavement applicable to North Road and Lindum Road conformed with the AS.
Turn lines
The AS 1742.14 (Manual of uniform traffic control devices Part 14: Traffic signals - Section 6 - turn lines), in part stated:
Turn lines may be used within major or complex intersections to indicate the proper course to be followed by turning vehicles. They shall be used within an intersection to assist separation of traffic in the case of multiple turning lanes for the one turn. They are not required when the path to be followed is obvious to drivers under all conditions.
A site inspection identified faded/worn turn lines painted on the road surface starting at the stop line on Lindum Road and curving to the right to connect with the edge of the painted median island at the entrance to the level crossing (Figure 6). The entrance span (left side of the roadway, adjacent to the boom barrier, to the edge of median island) connecting Lindum Road to the level crossing measured about 12 m. Whereas, the road span entering the level crossing from North Road measured about 3.5 m.
Figure 6: Gap between boom barrier tip and the median island Lindum Road approach, and faded turn lines
Source: Queensland Police Service, annotated by the ATSB
Managing safety at level crossings
Historical information
In 1997, the Queensland Government convened an inquiry into Brisbane’s Citytrain rail network. A focus of the inquiry was to provide recommendations to improve safety at railway level crossings. A conclusion from the inquiry stated:
Level crossings are critical road intersections which provide essential amenity to road users and rail travellers. The government has no strategies in place to determine risks at crossings and therefore to address level crossing safety in a planned and systematic way. A system to fund level crossings across the state according to risk is required. This will also require a comprehensive audit to determine the current risks at individual sites. This demands cooperative effort by Queensland Transport, Queensland Rail, the Department of Main Roads, and local authorities. The committee concludes that a state-wide level crossing safety strategy is required. Criteria for gauging risks and prioritising sites for protection upgrades is needed to guide future investments in level crossing protection to maximise safety dividends.
From this conclusion relevant recommendations were made:
• That Queensland Transport undertakes a comprehensive safety audit of railway level crossings in Queensland. This audit should compile information about their road vehicle and train speed limits; types and volumes of road vehicle and train traffic carried; road and environment conditions; types of protection installed; accident history; alignments; and other risk factors.
• That Queensland Transport devises a methodology to quantify risks at railway level crossings and allocate priority for investment in safety upgrades.
• That Queensland Transport devises a state-wide strategy for railway level crossing safety upgrades.
Risk assessment tool
In 1999, as a result of these recommendations a ‘risk scoring matrix’ was developed as an assessment tool used to identify key potential risks at level crossings and to assist in the prioritisation of crossings for upgrades. In 2002, the assessment tool was re-named as the Australian Level Crossing Assessment Model (ALCAM), and a national committee was established to ensure its consistency of development and implementation. In 2003, ALCAM was endorsed by the Australian Transport Council and adopted by all states and territories as well as New Zealand. Since its introduction, ALCAM has been regularly reviewed and modified. For example, in:
2004, an updated version was released
2006, the introduction of ‘flags’ to highlight areas representing high levels of risk
2007, changes to align with AS 1742.7 (Manual of uniform traffic control devices)
2014, the release of an updated version.
The ALCAM risk score comprised of 3 separate components: how physical properties at each site will affect human behaviours; the control type, vehicle (or pedestrian) volumes and train volumes; and the expected outcome in the event of a collision. The score is expressed in terms of an expected number of equivalent fatalities per year and allows for a comparison of level crossings within a given jurisdiction based on the level of risk. In turn, a priority list can be produced, which can be used to assist in the development of safety improvement programs (Australian Level Crossing Assessment Model, 2016).
Queensland Rail level crossing assessments
Queensland Rail initially surveyed its public level crossings between 2001–2002, using the risk scoring matrix assessment tool, producing an individual risk score rating of each level crossing as a baseline. Table 2 shows QR’s top 20 level crossings based on their risk score. All the level crossings are in south-east Queensland.
As noted in the table, 9 of the level crossings were re-assessed between 2004–2016 using the ALCAM, while the remaining 11 had not been re-assessed since their initial survey. Of the top 20 level crossings by risk score, the Kianawah Road level crossing was ranked sixteenth.
Table 2: Queensland Rail’s top 20 level crossings by risk score
No.
Level crossing
Initial survey
Risk score
Reassessment
1
Boundary Road
4 December 2001
161515190
11 September 2008
2
South Pine Road
11 December 2001
101835834
25 October 2016
3
Mackie Road
2 January 2002
99067968
12 July 2016
4
Oates Avenue
8 January 2002
94970766
5
Beenleigh Road
19 November 2001
87584304
6
Todd’s Road
8 January 2002
86299824
7
Beams Road
11 December 2001
80649355
8
Cavendish Road
6 December 2001
77831571
9
Dawson Parade
21 February 2002
72420707
10
Rowley Road
29 January 2002
63258456
11
Wacol Station Road
19 November 2001
60117406
15 August 2006
12
Nudgee Road
11 December 2001
59015500
13
South Pine Road
18 February 2001
57633975
8 February 2011
14
Osbourne Road
21 February 2002
56858762
6 October 2004
15
Samford Road
12 November 2001
52329280
19 February 2009
16
Kianawah Road
12 February 2002
46218266
17
Warrigal Road
4 December 2001
37685078
18
Sherwood Road
4 February 2001
37309859
6 October 2004
19
Nathan Road
4 December 2001
36079244
20
St Vincents Road
5 March 2002
35740814
3 October 2012
Other factors to mitigate risk
As noted in the ALCAM in Detail report (Australian Level Crossing Assessment Model, 2016) although the ALCAM is a comprehensive tool for the assessment of level crossing hazards, it cannot be applied in isolation. The authorities responsible for safety at level crossings need to understand the limitations of the ALCAM and recognise the wider external context in which the risks at individual level crossings will be managed. Therefore, rail and road managers (that is, state and local government agencies) also need to consider other factors and measures to mitigate risk at level crossings, which include:
risk assessments
collision and incident occurrence history
inspections and assessment history
results of audits and assurance activities
engineering experience (both rail and road)
local knowledge of driver or pedestrian behaviour
interface agreements
standards and best practice.
Safety management system
General
It was a legislative requirement of accreditation that rail transport operators (RTOs) and rail infrastructure managers (RIMs) have an appropriate safety management system in place. QR, as the RTO and RIM, had such a system comprising of a suite of policies, standards, procedures, documents, and agreements, which together constituted the means to manage below and above rail operations.
Queensland Rail’s level crossing safety standard
QR’s level crossing safety standard (MD-10-115) formed part of its safety management system. The standard stated:
Queensland Rail as the Rail Infrastructure Manager (RIM) shall conduct the actions as described within this standard and meet the intent of the Level Crossing Strategies of Queensland Rail, Queensland Level Crossing Safety Strategy and National Level Crossing Safety Committee.
At grade level crossings introduce an interface which presents an undesirable safety risk and additional complexity to the railway. The RIM shall control the risks of the Queensland Rail portfolio of level crossings ‘so far as is reasonably practical (SFAIRP) by the following actions:
• Explore opportunities for grade separation or closing level crossings and seek to minimise any proposals to construct a public level crossing on a greenfield site, with a clear objective to add no further open level crossings to the network (Queensland Level Crossing Safety Strategy, Strategy #9)
• Design and select appropriate level crossing locations and controls
• Construct crossings to approved designs by competent workers
• Assess risk, maintain and upgrade infrastructure as appropriate (Queensland Level Crossing Safety Strategy, Strategy #7)
• Monitor existing level crossings for changes to the risk and continue the assessment of risk through application of the Australian Level Crossing Assessment Model (ALCAM)
• Maintain level crossing infrastructure in accordance with Queensland Rail Standards and management of defects to an appropriate priority
• Determine measures to manage risks and seek to enter into an interface agreement with the road manager of that road
• Dispose of level crossings by denying access where controls have been removed, and removing level crossing infrastructure (lights, boom, signs, etc) where railways are closed.
This standard sets out a consistent level of control measures for the RIM to apply to all crossings on track managed by Queensland Rail, and the responsibilities and processes the RIM should use in order to minimise the risk of accidents at level crossings.
To maintain safety of its level crossings, QR was required to perform distinct types of inspections/assessments. Patrol and track inspections were conducted more frequently than assessments. The inspections were performed by maintenance staff who were trained to visually check the condition of the track infrastructure, level crossings and their associated components at regular intervals. Depending on the type of inspection and whether the level crossing had active or passive controls, the frequency of the inspection varied. If the level crossing had active controls, a patrol inspection occurred every 96 hours. If the crossing had passive controls, an inspection was required every 7 days. A track inspection was scheduled annually.
Unlike inspections, the criteria for level crossing assessments had a separate set of requirements and measures to evaluate safety. Assessors were specifically trained to conduct assessments in line with these requirements and measures. In accordance with QR’s level crossing safety standard (at the time of the accident), when conducting the assessment, the assessor evaluated the level crossing against the requirements of:
the approved design for the crossing
MD-10-575 Civil Engineering Track Standard
AS 1742.7 Manual of Uniform Traffic Control Devices Part 7: Railway Crossings
Queensland Department of Transport and Main Roads Manual of Uniform Traffic Control Devices (MUTCD)
MD-15-51 GSS Part 3 Signals and Level Crossings.
The assessment was to be undertaken by a level crossing assessor on a site inspection and measurements were to be taken in accordance with the following references:
Australian Level Crossing Assessment Model (ALCAM)
applicable inspection, detailed assessment or ALCAM data collection forms (completed by field survey) and assessment process
Version 1.0 of QR’s level crossing safety standard released July 2010, and version 2.0 released June 2012, stated:
Risk assessments of public and pedestrian level crossings must be carried out in conjunction with the road authority. A joint recommendation must be made on the control measures appropriate to the level crossing, to adequately control the risks identified.
The level of protection required at the level crossing must be determined taking into consideration:
• the recommendation provided by the QT risk assessment matrix
• local knowledge including consideration of other site and surrounding specific conditions and problems that could affect the safety of the crossing. For pedestrian crossings this will include the proximity of schools, retirement villages, institutions, etc
• vehicle and typical pedestrian behaviour at the crossing
• minor improvements that would increase the level of safety.
Version 3.0 of the level crossing safety standard released March 2016, and version 3.1 released November 2017, stated:
All public level crossings and pedestrian crossings in the Queensland Rail network shall [mandatory] be assessed using a recognised level crossing risk assessment model, i.e. the Australian Level Crossing Assessment Model (ALCAM). Proposed new public level and pedestrian crossings shall be assessed using ALCAM as part of the approval process.
Queensland Rail will review public and pedestrian level crossings at least once every five years unless other changes to the crossing conditions require an assessment sooner. Responsible Road Managers will be invited to take part in these inspections in accordance with the relevant IA [interface agreement]. These inspections [assessments] shall be carried out to ensure the existing controls are still effective, ensure continuing compliance with the controls approved following the initial assessment for the crossing, and to verify that the conditions applying at the time of the initial assessment are still current.
Version 4.0 on the level crossing safety standard, released April 2020 and current at the time of the accident, stated:
The Asset Manager [QR] shall conduct assessments on all types of level crossings including, public, pedestrian, private, maintenance and temporary construction level crossings. These assessments shall include track inspections, signalling equipment servicing, level crossing assessments and detailed level crossing assessments.
It further stated:
Level Crossing Assessments and Detailed Level Crossing Assessments of public level crossings and public pedestrian crossings shall [mandatory] be assessed using the Australian Level Crossing Assessment Model (ALCAM). Proposed new public level and pedestrian crossings shall be assessed using ALCAM as part of the approval process.
Table 3 provided information on QR’s level crossing inspection and assessment process.
Table 3: Types of inspection/assessment of level crossings
Type
Conducted by
Purpose
Frequency
How
Patrol inspection
Road patroller
safety of rail traffic operations
96 hours active
7 days passive
Visual
Track inspection
Track inspector
safety of rail traffic operations
Annually
Walking
Level crossing assessment
Level crossing assessor
controls are in place and complete check for changes in traffic or context
5 years
On-site
Detailed assessment
Level crossing assessor
confirm the risk score rating of the crossing
as required by incident or other assessment findings
on-site ALCAM public level crossing
Resource availability
It was a requirement of an RTO/RIM to ensure it had systems and procedures for estimating the resources, including people and equipment needed to operate and maintain railway operations and to implement, manage and maintain its safety management system.
As previously mentioned, all versions of QR’s level crossing safety standard, since the release of version 3.0 in March 2016, noted that all public and pedestrian level crossings would be assessed using the ALCAM assessment tool. The standard also stated that level crossings would be assessed by a qualified assessor at the level crossing site at least once every 5 years. At that time, QR was responsible for the assessment of at least 1,138 public level crossings, and related pedestrian crossing if applicable.
Between 2016–2021, QR had one assessor qualified to conduct level crossing assessments. To comply with the level crossing safety standard, it meant the assessor was required to assess 227 public level crossings each year. In addition, the assessor was also required to assess pedestrian, private, maintenance and temporary construction level crossings according to the requirements of the standard. Information provided by QR, showed that during this time only 52 public level crossing assessments were conducted, which averaged 10 assessments per year.
Interface agreement
Prior to the introduction of the Rail Safety National Law (RSNL) Queensland in 2017, rail in Queensland was regulated by the provisions of the Transport (Rail Safety) Act 2010, and its supporting regulation. Both the past Act and the current Law required RIMs and road managers to identify risks to safety arising from rail or road crossings, determine measures to manage, so far as is reasonably practicable, those risks and seek to enter into an interface agreement.
According to the legislation, there was to be a written agreement between the relevant parties articulating the risk management process and framework necessary to identify and assess risks and have documented accountabilities/responsibilities of each party. According to the RSNL, and in part the superseded Transport (Rail Safety) Act 2010, an interface agreement was to include provisions for:
implementing and maintaining measures to manage risks identified under section 99(1)(c) associated with the interface
the evaluation, testing and (where appropriate) revision of measures in relation to identified risks and incidents considered
the respective roles and responsibilities of each party to the agreement in relation to those measures
procedures, by which each party to the agreement will communicate, monitor, and determine whether the other party complies with its obligations under the agreement
a process for keeping the agreement under review and its revision.
The guidance material from the Office of the National Rail Safety Regulator, relevant to the development of an interface agreement, indicated that this requirement could be conducted by performing risk assessments.
Section 109 of the RSNL (Identification and assessment of risks) stated:
A rail transport operator, rail infrastructure manager or road manager that is required under this Subdivision to identify and assess risks to safety that may arise from operations carried out by another person may do so—
(a) by itself identifying and assessing those risks; or
(b) by identifying and assessing those risks jointly with the other person; or
(c) by adopting the identification and assessment of those risks carried out by the other person.
As mentioned, with the introduction of the Transport (Rail Safety) Act 2010, there was a requirement for RIMs and road managers to seek to enter into interface agreements. A provision in the Act allowed for a 2-year transition period to progress the requirements necessary for this to occur.
During the transition period, there was limited coordination between QR and the BCC to progress an interface agreement. However, just short of the 2-year transition period, on 23 August 2012, QR supplied BCC a draft copy of an interface agreement for consideration.
In the following years there were multiple meetings and discussions between QR and the BCC in order to progress the agreement, however, outstanding matters between the 2 parties blocked its enactment. During the negotiations, the state rail regulator (prior to 2017), and the Office of the National Rail Safety Regulator (after 2017), communicated with both parties in order to finalise the agreement. Nonetheless, unresolved matters between the 2 parties continued to hinder the progress of the agreement for many years after. At the time of the accident there was no interface agreement in place.
Queensland Rail’s level crossing safety standard (version 4.0) current at the time of the accident, stated:
If an interface agreement has not been accepted, the Asset Manager [QR] shall take reasonable steps to manage the safety of the level crossing to meet the requirements of the RSNL and making use of powers from the Transport Infrastructure Act 1994 (Queensland).
The previous versions of QR’s level crossing safety standard (version 3.0 and 3.1) also stated:
If an interface agreement has not been agreed to, the responsibilities for managing level crossing safety shall be in accordance with the Transport Infrastructure Act 1994, unless there are other documented local procedures in place.
Safety analysis
Introduction
The driver and sole occupant of a small red motor vehicle was fatally injured after colliding with a suburban passenger train at the Kianawah Road level crossing in Brisbane, Queensland. The occupants of the train, the driver and guard, were not injured and there was only minor damage to the train.
At the time of the accident, the protection devices at the level crossing (half boom barriers and flashing lights) operated as the train approached.
This analysis will discuss the driver’s actions approaching and entering the intersection, the complexities of the intersection adjacent to the level crossing, and how conditions at the rail-road interface were confusing to road users. The length of the lowered boom barrier on the northern side of the Kianawah Road level crossing will also be examined. Further, it will discuss how risk at the crossing was not being managed in accordance with Queensland Rail’s (QR’s) safety management system, and the implications of QR and the Brisbane City Council not entering into a road-rail interface agreement in a timely manner.
Approaching and entering the level crossing
It was reported that the driver of the small red motor vehicle may not have been familiar with the intersection and was possibly using a navigation system to assist them with directions to their destination. As they travelled along Lindum Road towards the Lindum Road – North Road intersection they passed road signage (RX-7 assembly) providing information/advice of the upcoming level crossing. While it was unknown if the signage was fully intact at that time, the sign depicting the approaching level crossing was in situ and the driver was subsequently observed stationary at the stop line of Lindum Road.
The ATSB had considered if the driver was aware of the approaching intersection and adjacent level crossing, and whether their view of the flashing signal assembly (RX-5) on the opposite side of the intersection was obscured by other vehicles. However, there was insufficient evidence available to establish these factors.
After advancing to the front of the queue, and while stationary at the stop line, the protection devices of the level crossing were active, and the boom barriers had started to lower. At that time, the driver of the motor vehicle was observed actively looking in either direction for opposing road traffic. However, the ATSB could not determine whether the driver was aware of the active protection devices of the level crossing, if they had discounted them, or considered they did not apply to the passage of their vehicle.
Despite this, closed-circuit television footage and witnesses observed the vehicle move off from the stop line when a break in traffic became available. From the available evidence, it was very likely the vehicle followed the turn line markings on the road past the end of the lowered boom barrier into the path of the approaching train.
Complexity of road-rail interface
The intersections on either side of the Kianawah Road level crossing and the level crossing itself had a history of incident/accident occurrences. This was evidenced by the records provided by QR, which showed that, between December 2015 and February 2021, the level crossing had the fifth highest incident/accident numbers in south east Queensland. Likewise, for many years, residents have raised safety concerns relevant to the intersections and the adjoining level crossing.
Problems that existed for motorists using the Lindum Road turn-right lane was that it merged with North Road, Kianawah Road and the rail corridor at the level crossing. This created a condition where traffic from Lindum Road approached the entrance to the level crossing at a 40° angle, forming a significant 12 m wide entrance to the level crossing, as illustrated in Figure 3. This, and traffic activity connecting the various access roads at the intersection created complexity for road users. To reduce the complexity and driver confusion, turn line markings were painted on the road pavement connecting the stop line and the painted median island guiding road users from Lindum Road through the level crossing.
These details were consistent with the findings of the study initiated by the state government, and information provided by the Department of Transport and Main Roads, which concluded that the intersections adjacent to the level crossing were complex and difficult to navigate for motorists.
The study also reported that driver confusion and frustration at the intersections, particularly for motorists turning right from the side roads (Lindum Road and Sibley Road), was contributing to incidents/accidents between road vehicles at the intersections or between road vehicles and trains at the level crossing. This was more problematic in peak times or busy periods when traffic activity (both road and rail) intensified, therefore minimising the opportunity for road users to turn right from the side roads and pass through the crossing. Some local residents said that they would avoid the intersection due to delays and safety concerns.
The number of reported occurrences at the level crossing, the feedback received from road users, and the work undertaken by governments, all indicated that the road-rail interface at the Kianawah Road level crossing was complex and visually noisy from a road user’s perspective. Although the accident occurred outside peak periods, there was still sufficient road traffic at the intersection to heighten driver workload.
Boom barrier irregularity
In accordance with the Australian Standard 1742.7, (Manual of unform traffic control devices Part 7: Railway crossings), the boom barrier on the northern side of the Kianawah Road level crossing was to extend from the left-side of the roadway to the edge of the median island that separated traffic lanes. Its function was to block road traffic from North Road and Lindum Road when the level crossing was active. However, the boom barrier was too short and did not extend to the median island, forming a gap between the tip of the boom barrier and the median island.
The gap had no effect on road traffic approaching the crossing from North Road, as the boom barrier completely blocked road traffic from entering the level crossing. However, the 3.1 m gap between the tip of the boom barrier and the median island meant that the barrier only partially blocked road traffic that approached the level crossing from Lindum Road.
This was exacerbated by the turn line markings on the road pavement, although faded, which directed traffic towards the gap. These factors combined increased the risk of road users turning right from Lindum Road and bypassing the boom barrier while the crossing was active, which occurred on the day of the accident and could occur in vehicles as wide as a typical bus.
Another 29 locations were also identified with inconsistencies regarding the requirements for boom barriers, as stipulated in the Australian Standard.
Level crossing risk not managed
To constantly maintain safety, it is crucial that rail infrastructure managers commit to the ongoing risk management process, particularly at the road and rail interface of level crossings, which are well known for their high-risk consequences. The purpose of a level crossing assessment was to ensure that the existing controls were still effective, ensure continuing compliance with the controls approved following the initial assessment for the crossing, and to verify that the conditions applying at the time of the initial assessment were still current.
In 2001–2002, QR surveyed all their level crossings using the ‘risk scoring matrix’ as a standardised assessment tool to identify potential risks at crossings and to assist in the prioritisation of crossing upgrades. The results of these assessments were to establish a baseline for future assessments.
QR’s intent was to manage risks at level crossings through the process of monitor and review using the Australian Level Crossing Assessment Model. This thinking was captured in their level crossing safety standard. The standard provided the minimum safety requirements of level crossings, which included the assessment of level crossings, responsibilities of the rail infrastructure managers, the processes to be used to minimise the risk of accidents at level crossings and having an interface agreement with the road manager. The standard was part of the QR safety management system.
The provisions of QR’s level crossing safety standard, over time, has continued to meet the needs of the past Transport (Rail Safety) Act 2010 and the current Rail Safety National Law (Queensland) from a safety perspective. The content material within the standard has continued to define the requirements and measures necessary to mitigate risk at level crossings. This included assessing public and pedestrian level crossings at least once every 5 years unless other changes to the crossing conditions required an assessment sooner.
The Kianawah Road level crossing was initially assessed for risk in February 2002. Records provided by QR showed that, at the time of the accident, some 19 years after its initial assessment, the level crossing had not been reassessed. Likewise, the ATSB also identified other level crossings within south east Queensland, some of them with high-risk scores and records of high incident/accident rates, which had not been reassessed since their initial assessment more than 20 years ago.
Had QR reassessed the Kianawah Road level crossing in accordance with their level crossing safety standard, it was very likely that the 3.1 m gap between the tip of the boom barrier (in its lowered state) and the median island, and the irregularity of the turn line markings on the road pavement guiding road users through that gap, would have been detected and rectified. Similarly, there were missed opportunities to identify that a further 29 level crossings had similar issues where the lowered boom barriers did not comply with the requirements of AS1742.7 Manual of Uniform Traffic Control Devices Part 7: Railway Crossings.
Insufficient resources to assess safety at level crossings
The purpose of level crossings assessments is to determine whether the control measures in place at the last assessment are still effectively managing the risks unique to that location. It is important to identify any new hazard/s or hazard/s that may not have been identified at the last assessment.
Equally important is that the organisation has sufficient resources available to ensure assessments are conducted within the required timeframes. These assessments, if conducted in accordance with QR’s level crossing safety standard, provided assurance that risks at level crossings were being managed as far as is reasonably practicable.
Between 2016–2021, QR had one person appropriately qualified to assess all public, private, pedestrian, maintenance, and temporary construction level crossings within the rail network.
Records provided by QR showed that only 52 of the 1,138 public level crossings on the rail network were assessed over this 5-year period. Of the top 20 level crossings, according to their risk scores, just 2 were assessed. The QR level crossing safety standard stated that an on-site level crossing assessment of all crossings should be conducted every 5 years. However, based on the total number of level crossings, this task was impossible given the resources available.
Consequently, a substantial proportion of QR level crossings were not being assessed in accordance with its level crossing safety standard due to the lack of resources. In this case, it meant that the Kianawah Road level crossing had not been assessed since 2002, which was a missed opportunity to identify that the length of the boom barrier did not extend to the median island as required by the Australian Standard.
No interface agreement
Managing the risks of the road-rail interface was a shared responsibility between road authorities and rail infrastructure managers, formalised through an interface agreement. These agreements for public roads provided an opportunity for the relevant parties to conduct risk assessments, to identify and evaluate the risks at the interface, and control and maintain them through a systematic process. This established a coordinated approach to ensure risks at respective level crossings were identified and controlled.
Protracted negotiations between QR and the Brisbane City Council had commenced in 2012 and were ongoing. As a result, at the time of the accident, there was no interface agreement in place. Consequently, in accordance with QR’s level crossing safety standard, they were to take reasonable steps to manage the safety of the crossing. Other than the original assessment of the Kianawah Road level crossing in February 2002, there were no records indicating that further assessments had been conducted on the level crossing. However, having an interface agreement in place at this location was particularly important given the complexity of the road and rail interface. In this case, had there been an agreement, the associated risk assessment would have likely identified the problem with the boom barrier length and corrective action would have resolved the matter.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to a level crossing accident between an express suburban passenger train and road vehicle at Kianawah Road level crossing, Wynnum West, Brisbane, Queensland, on 26 February 2021.
Contributing factors
The road user very likely followed the turn line markings on the road surface directing them past the end of the lowered boom barrier onto the level crossing into the path of the approaching train.
The road-rail interface at the Kianawah Road level crossing was complex and visually noisy. This increased the risk of driver (vehicle) confusion and the potential for vehicle-train collisions.
Contrary to the relevant Australian Standard, there was a 3.1 m gap between the tip of the lowered boom barrier and the median island on the northern side of the Kianawah Road level crossing. With the turn line markings directing traffic towards the gap, this increased the risk of road users turning right from Lindum Road and bypassing the boom barrier while it was active. (Safety issue)
Although Queensland Rail’s internal standard required safety assessments of each public level crossing at least every 5 years, there had been no review or assessment of the Kianawah Road and other level crossings since 2001–2002. (Safety issue)
Queensland Rail had insufficient resources available to assess all 1,138 public level crossings at 5 yearly intervals or sooner as required by its level crossing safety Standard, with only one person qualified to conduct level crossing safety assessments. (Safety issue)
There was no formal interface agreement between Queensland Rail and the Brisbane City Council to jointly identify and manage ongoing and changing safety risks at the road and rail interfaces. (Safety issue)
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the rail industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: Contrary to the relevant Australian Standard, there was a 3.1 m gap between the tip of the lowered boom barrier and the median island on the northern side of the Kianawah Road level crossing. With the turn line markings directing traffic towards the gap, this increased the risk of road users turning right from Lindum Road and bypassing the boom barrier while it was active.
Safety issue description: Although Queensland Rail’s internal standard required safety assessments of each public level crossing at least every 5 years, there had been no review or assessment of the Kianawah Road and other level crossings since 2001–2002.
Insufficient resources to assess safety at level crossings
Safety issue description: Queensland Rail had insufficient resources available to assess all 1,138 public level crossings at 5 yearly intervals or sooner as required by its level crossing safety Standard, with only one person qualified to conduct level crossing safety assessments.
Safety issue description: There was no formal interface agreement between Queensland Rail and the Brisbane City Council to jointly identify and manage ongoing and changing safety risks at the road and rail Interface.
Glossary
ALCAM
Australian Level Crossing Assessment Model
AS
Australian Standard. Standards are developed either by a national standards body (like standards Australia) or other accredited bodies. Any standards developed under the Australian Standard® name have been created in Australia or are adoptions of international or other standards.
BCC
Brisbane City Council. A local government in the state of Queensland.
QR
Queensland Rail. A rail transport operator and rail infrastructure manager in the state of Queensland.
RIM
Rail infrastructure manager. Means the person who has effective control and management of the rail infrastructure, whether or not the person owns the rail infrastructure or has a statutory or contractual right to use the rail infrastructure or to control, or provide, access to it.
RSNL
The Rail Safety National Law. The purpose of the Law is to provide safe railway operations in Australia.
RTO
Rail transport operator. An organisation or entity that is a rail infrastructure manager or a rolling stock operator or both.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Queensland Police Service
Queensland Rail
Queensland Department of Transport and Main Roads
train driver of service E820
Office of the National Rail Safety Regulator
witnesses
closed-circuit television footage from Lindum Station and E820
event recorder data.
References
Australian Level Crossing Assessment Model (2016). ALCAM in Detail: An Introduction to the new ALCAM models (2014).
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
Queensland Rail
Brisbane City Council
train driver of service E820
Office of the National Rail Safety Regulator.
Submissions were received from:
Queensland Rail
Brisbane City Council
Office of the National Rail Safety Regulator.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Up line: the rail line that facilitates train movements in an easterly direction towards Cleveland.
[2] Universal traffic control: A system unique to Queensland Rail that assists network control officers safely route and monitor the movement of trains.
[3] The train had 2 horns: town and country. The country horn was the louder of the 2 and would be sounded when approaching level crossings.
[4] Whistle boards: are located at places where it is necessary for the driver to sound the horn. For example, level crossings, bridges, or tunnels.
[5] The train driver’s recall of the vehicle ‘travelling at a slow and consistent speed’ was consistent with speed calculations undertaken by the ATSB from the front of train closed-circuit television footage.
[6] Austroads Guide to Road Design (2021) Part 3: Geometric Design.
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
At about 1340 on Friday 26 February 2021, a non-revenue express suburban train collided with a road vehicle at Kianawah Road level crossing, adjacent to Lindum Station on the Cleveland line in Wynnum West, a suburb of Brisbane, Queensland.
The road vehicle was a small 4-door hatchback (Hyundai i20). The driver was from the Sunshine Coast and was visiting a friend in Brisbane. At about 1330, the driver left the friend’s address to visit a location in Wynnum. The friend stated that the driver was unfamiliar with the area and the level crossing and it was likely that they used a navigation system to assist with directions.
The hatchback travelled in an easterly direction along Lindum Road. At the T-intersection of Lindum Road and North Road, the driver’s intention was to turn right and pass though the Kianawah Road level crossing en route to Wynnum (Figure 1).
Figure 1: Driver’s intended route from Lindum Road through the level crossing
Source: Google Earth, annotated by the ATSB
As the hatchback approached the Lindum Road–North Road intersection, there were two cars waiting in a queue in the turn right lane. During a pause in traffic, the first of the two cars turned right and passed through the level crossing. At that point in time, the express train, travelling in an easterly direction towards Cleveland, automatically activated the level crossing protection on its approach.
As the second car ahead of the hatchback moved away from the ‘stop line’ to turn right, the flashing lights on the opposite side of Lindum Road were operating, warning of the train’s approach. As that car passed through the level crossing, the boom barriers were lowering.
After the second car moved away from the intersection, the driver of the hatchback moved forward on Lindum Road and stopped at the intersection ‘stop line’. The driver delayed at the ‘stop line’ to give way to another car that was travelling south along North Road. This car turned right into Lindum Road in front of the hatchback. The driver then momentarily moved forward but came to a sudden stop as another car (a utility vehicle) approached the intersection from the same direction.
The driver of the utility vehicle stated that, as they turned right into Lindum Road, they observed the boom barrier was horizontal and saw a train approaching the level crossing. As they looked through their rear-view mirrors, they noticed that the hatchback which had been stopped at Lindum Road had moved off and was approaching the level crossing. They witnessed the car pass onto the level crossing and collide with the train.
Evidence from station closed-circuit television (CCTV) footage showed that the hatchback passed to the right of the boom barrier’s lowered arm, and to the left of the turn line from Lindum Road to Kianawah Road. The hatchback was destroyed, and the sole occupant was fatally injured. The train sustained minor damage and the only two occupants of the train, the driver and guard, were not injured.
Context
Level crossing general information
The Office of the National Rail Safety Regulator (ONRSR) stated in its Rail Safety Report 2019–2020:
There are more than 23,000 level crossings in Australia and at all of them there exists a level of risk to safety – indeed, other than suicide and trespass, accidents at level crossings are the primary cause of railway related fatalities among the general public.
There were 37 level crossing collisions between a freight train, passenger train or tram and a road vehicle reported in the 2019–2020 financial year, the majority of which involved a freight train. More than 60% of these collisions occurred at crossings protected by active control devices, such as bells, lights and boom gates. There were three fatalities [from two accidents] and two serious injuries reported as a result of these collisions, all affecting road vehicle occupants.
There were 6 level crossing collisions between a freight train, passenger train or tram and a person reported in the 2019–2020 financial year, resulting in four serious injuries to members of the public. Five of the six collisions took place at crossings protected by active control devices.
All rail safety stakeholders, including the general public, have a role to play in improving safety at level crossings and ONRSR continues to advocate for co-operation between all parties that will ultimately help reduce the rate of fatalities and serious injuries. ONRSR also continues to support the work being done by governments and industry to remove level crossings and their commitment to a policy of no new level crossings.
According to the Queensland Rail (QR) website:
In Queensland, there are over 1,200 level crossings that are connected to the road network. Level crossing incidents carry a high risk of serious injury or death. That is why signs and signals are in place to keep everyone safe. All level crossings have some form of protection including:
- Flashing lights - Flashing lights and Boom gates - Stop or Give Way signage - pedestrian crossing gates - warning signs…
In the 2019-2020 financial year, Queensland Rail recorded seven collisions in Queensland. In addition, there were 211 near miss incidents with 133 in South East Queensland (SEQ) and 78 in regional areas.
Kianawah Road level crossing design
QR was the rail infrastructure manager for the Cleveland rail line (and the rest of the Brisbane suburban rail network), including the rail infrastructure at the Kianawah Road level crossing. The Brisbane City Council (BCC) was the road manager for the roads surrounding the Kianawah Road level crossing.
The Kianawah Road level crossing is in Wynnum West, in the eastern suburbs of Brisbane. Kianawah Road runs in a northerly direction up to the rail corridor, and North Road runs in a southerly direction up to the rail corridor. Kianawah Road and North Road cross the rail corridor at a 40° angle. The roadway is about 13 m wide with one lane in each direction and a painted median island between the two lanes.
The level crossing had active control devices in place that were designed to control the movement of vehicular and pedestrian traffic through the crossing. These devices included level crossing flashing signals, boom barriers, and audible warning alerts. The devices were designed to activate prior to and during the passage of a train through the level crossing.
There was no requirement for a road user approaching the crossing on Kianawah Road or North Road to stop when the level crossing protections were not active. If the protections were active, road users were required to stop at ‘stop lines’ painted on the road in front of the boom barriers (Figure 2).
In the immediate area of the level crossing, there were two T-intersections, one on either side of the crossing. On the northern side, Lindum Road connected with North Road, and on the southern side, Sibley Road connected with Kianawah Road.
There was a stop sign on Lindum Road where it joined North Road, and a stop sign on Sibley Road where it joined Kianawah Road. Traffic flow was such that a vehicle turning right from Lindum Road to cross the level crossing (as was the case during the accident sequence) had to stop and give way to traffic from both North Road and Kianawah Road (Figure 2).
Figure 2 shows the Lindum Road and North Road intersection on the northern side of the level crossing and the Kianawah Road and Sibley Road intersection on the southern side of the crossing. Depicted in the image are the potential variations in road vehicle travel, the path of the vehicle involved in the accident, the direction of the train’s travel and the point of the collision.
The position of the two boom barriers on North Road and Kianawah Road are also indicated in Figure 2. The road surface was painted with yellow cross-hatched lines in the area between the two boom barriers. Level crossing flashing signals were positioned on the northern side to face road vehicle users approaching the crossing from North Road. There was also a set of flashing lights positioned to face road users approaching the crossing from Lindum Road (Figure 3).
Australian Standard (AS) 1742.7 – Manual of uniform traffic control devices (Part 7: Railway crossings) stated that:
Boom barriers shall comprise as a minimum, a boom extending from the left side of the roadway–
(a) to the right hand kerb or edge of a one-way roadway;
(b) to the edge of a median island; or
(c) in the case of a two-way roadway, to the dividing line or centre of the roadway if no line is marked.
The boom in its lowered state should be placed at right angles to the road centre-line.
A post-accident assessment of the Kianawah Road level crossing was conducted by the Queensland Police Service forensic crash unit. It identified that the boom barrier on the northern side, which protected vehicular traffic from entering the level crossing from Lindum Road, was 10 m long and did not extend to the edge of the painted median island or to the centre of the roadway which divided the two-way roadway. The gap between the edge of the median island and the tip of the boom barrier when in its lowered state was 3.1 m (Figure 3).
In comparison, the width of a general traffic lane in an urban environment is between 3.0 and 3.5 m. The width of the road vehicle involved in the accident was about 1.8 m. In other words, a normal road vehicle could turn right from Lindum Road on the correct side of the turn line and easily pass to the right of the lowered boom barrier (as occurred in the case of this accident).
Figure 3 shows the gap between the end of the boom barrier and the edge of the median island, if approaching the level crossing from Lindum Road. The yellow arrows indicate the white painted turn line markings, which had been worn due to vehicle activity.
In contrast, there was no gap between the boom barrier and the centre of the roadway on the southern side of the level crossing (that is, the approach from Sibley Road).
Figure 3: Gap between Lindum Road to Kianawah Road turn line and the boom barrier
Source: Queensland Police Service, annotated by the ATSB
Activation of level crossing protection devices
Under normal conditions, the level crossing protection devices will activate when the signalling system detects an approaching train. On the day of the accident, the universal traffic control (UTC) replay recorded the flashing light signals at the level crossing were operating for about 8 seconds before the boom barriers started to lower. The boom barriers took about 12 seconds to lower from vertical to the horizontal position.
Lindum Station CCTV footage showed that the boom barrier was in its lowered state for about 10 seconds before the hatchback passed onto the active crossing. The train arrived at the level crossing about 12 seconds after the boom barriers lowered to the horizontal position.
Based on the available evidence, the active control devices at the level crossing functioned as designed immediately prior to the accident.
The maximum allowable speed for a train passing through the crossing was 100 km/h. The train involved in the accident was travelling below the maximum speed, and the train driver complied with all relevant requirements on approach to the crossing.
Reported occurrences at Kianawah Road level crossing
According to QR data, there have been numerous reported incidents at the Kianawah Road level crossing involving road vehicles passing through the crossing after the protection had activated. More specifically, during the 2-year period from March 2019 to February 2021, there were:
5 reports by train drivers of applying emergency braking due to a road vehicle passing through the crossing with the boom barriers down
5 reports where a boom barrier had been hit by a road vehicle
6 reports where a boom barrier had come down on top of a vehicle
14 reports of a road vehicle passing through the crossing while the boom barrier was already down
9 reports of a road vehicle passing through the crossing while the boom barrier was coming down
5 reports of multiple vehicles passing through the crossing while the boom barrier was coming down
9 reports of multiple vehicles passing through the crossing while the lights were flashing.
Given the nature of the reports involving multiple vehicles, it is likely that the number of vehicles passing through the crossing after the lights were activated and/or the boom barrier started descending was much higher than reported. There was insufficient detail in most reports to determine how many events were associated with vehicles entering the crossing from Lindum Road.
In the same period, there were also numerous reports of pedestrians passing through the pedestrian gates at the crossing when they were closed. In February 2019, a pedestrian was struck and fatally injured by a train at the level crossing.
Over a period of many years, members of the public had raised safety concerns associated with the level crossing.
Level crossing assessments
The Australian Level Crossing Assessment Model (ALCAM) is an assessment tool used to identify hazards and risks at level crossings, and to assist the prioritisation of level crossing upgrade. It is a comprehensive tool for the assessment of level crossing hazards, but it cannot be applied in isolation. Any risk assessment and treatment also needs to consider other factors such as collision / near-collision history, local knowledge of driver behaviour, engineering experience (both rail and road), and relevant standards and best practice.
QR advised that its last ALCAM assessment of the Lindum Road level crossing was conducted in 2002. An additional assessment of the pedestrian crossing aspects was conducted in 2019, following the fatal pedestrian accident.
In November 2019, the Queensland Department of Transport and Main Roads initiated a study to investigate options to improve safety in the Lindum Station precinct for road users and the local community. The study was jointly funded by the Commonwealth Department of Infrastructure, Transport, Regional Development and Communications.
Interface coordination responsibility at level crossings
The Rail Safety National Law (RSNL) established a shared responsibility for safe railway operations at level crossings. More specifically, section 107 of the RSNL (Queensland) stated:
(1) A rail infrastructure manager must—
(a) identify and assess, so far as is reasonably practicable, risks to safety that may arise from railway operations carried out on or in relation to the manager's rail infrastructure because of, or partly because of—
(i) the existence of road infrastructure of a prescribed public road; or
(ii) the existence or use of any rail or road crossing that is part of the road infrastructure of a public road; and
(b) determine measures to manage, so far as is reasonably practicable, those risks; and
(c) for the purpose of managing those risks—seek to enter into an interface agreement with the road manager of that road…
(2) The road manager of a public road must—
(a) identify and assess, so far as is reasonably practicable, risks to safety that may arise from the existence or use of any rail or road crossing that is part of the road infrastructure of the road because of, or partly because of—
(i) the existence of road infrastructure of a prescribed public road; or
(ii) the existence or use of any rail or road crossing that is part of the road infrastructure of a public road; and
(b) determine measures to manage, so far as is reasonably practicable, those risks; and
(c) for the purpose of managing those risks—seek to enter into an interface agreement with the rail infrastructure manager of the rail infrastructure.
Under section 105, the requirements for an interface agreement included:
(a) implementing and maintaining measures to manage risks identified under section 99(1)(c) associated with the interface; and
(b) the evaluation, testing and (where appropriate) revision of measures in relation to identified risks and incidents considered; and
(c) the respective roles and responsibilities of each party to the agreement in relation to those measures; and
(d) procedures by which the parties to the agreement will exchange information about, and monitor compliance with, their obligations under the agreement; and
(e) a process for keeping the agreement under review and its revision.
The requirements for interface agreements had been in effect in Queensland since 2012.
Although there had been a significant amount of correspondence between QR and the BCC regarding a level crossing interface agreement, no interface agreement relevant to the Kianawah Road level crossing and the majority of other level crossings had been formalised at the time of the Kianawah Road level crossing accident on 26 February 2021. However, a small number of site-specific interface agreements had been entered into (for example, between BCC and Airtrain Citylink).
Safety action
Prior to the public release of the Preliminary report, Queensland Rail (QR) and the Brisbane City Council (BCC) advised of the following proactive safety actions they had undertaken and/or are undertaking:
QR undertook a post-incident updated level crossing assessment (using ALCAM), completed on 2 March 2021.
QR and BCC formalised a level crossing interface agreement to encompass all level crossings in the BCC area (signed on 4 August 2021).
As a result of QR monitoring of near-miss data, two active interventions have been triggered with the Queensland Police Service (QPS) at the Kianawah Road level crossing; one in August 2019 (targeting pedestrian and vehicle breaches) and one in June 2020. QR continue to work closely with the police in regard to driver behaviour at the crossing.
BCC, QR and the Department of Transport and Main Roads are participating in the Lindum Station Precinct Study. This study is reviewing interim, short-term and long-term options for the level crossing.
QR has commenced engineering activities to source and trial usage of a longer boom barrier than the one currently installed on the northern side of the Kianawah Road level crossing.
Further investigation
The investigation is continuing and will include further assessment of:
the recorded data and the sequence of events leading up to the collision
the design of the Lindum Road level crossing and its similarity to any other level crossings
maintenance activity associated with the level crossing and approach roads
history of inspections by the rail infrastructure manager and road manager relevant to managing risks at the level crossing
incident/accident history at the level crossing and connecting intersections
risk assessments conducted of the level crossing and the processes for conducting such assessments
the assurance activities conducted by the rail infrastructure manager and the road manager relevant to risk at level crossings, including the development of an interface agreement.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
This investigation was conducted under the Transport Safety Investigation Act 2003 (Commonwealth) by the Office of Transport Safety Investigations (NSW Government) on behalf of the ATSB in accordance with the Collaboration Agreement. Released in accordance with section 25 of the Transport Safety Investigation Act 2003.
Executive summary
Source: Fire and Rescue NSW
What happened
On 24-25 February 2021, freight train 4BM4 operated by Pacific National (PN) was scheduled to travel from Brisbane, Queensland to Melbourne, Victoria. The train was crewed by two drivers and consisted of three locomotives and 37 wagons.
During the journey, the crew of train 4BM4 experienced heavy rainfall that became more intense the further south they travelled into New South Wales (NSW).
The driver of 4BM4 reported that after departing Kungala (between Grafton and Coffs Harbour in NSW) there was heavy rain and large amounts of water around the rail corridor. After passing Glenreagh they noticed water approaching the rail line that was building up near the rail head about 1‑1.5 km before the derailment site. They had recently passed a freight and passenger service that had been through the area but had not been advised of any issues so continued. On exiting a curve on approach to Nana Glen, a section ahead of the train had been washed away at 643.800 km. The drivers did not see the washaway but due to speed and sighting distance they would not have been able to stop if they had.
At 0137, the train passed over the washaway while travelling at approximately 59 km/h and derailed. The first and third locomotives derailed with the third locomotive coming to rest on its side. Ten wagons derailed, some of the wagons entered floodwaters on both sides of the rail line. During the derailment, the second driver received minor injuries and the fuel tank on the second locomotive was damaged and leaked. There were dangerous goods on the train, but they were not involved in the derailment.
There was significant damage to the rail line, rolling stock and freight. The rail line reopened after nine days once flood water had receded, rolling stock was removed and the track was repaired.
What the ATSB found
The network users were not aware of the extent of the severe weather event and had not been advised of an amber alert issued by the weather monitor Early Warning Network (EWN) prior to the derailment. Australian Rail Track Corporation (ARTC) and PN did not provide guidance for train crew on how to respond to extreme wet weather events or floodwater in the rail corridor. There was no guidance for when trains should stop or report if there was water on the track formation, covering the ballast, sleepers or the rail. Neither driver of two previous trains which passed through the section at 0054 and 0110 reported a condition affecting the network (CAN), relating to the poor weather conditions in the vicinity of Nana Glen, to the ARTC network controller. And, although visibility was severely affected, the drivers of all involved services did not slow their trains which reduced their opportunity to sight potential obstructions and safely traverse level crossings.
The culvert located nearest to the derailment at 643.849 km did not have sufficient capacity to discharge the runoff from the rain event on the night of 24-25 February 2021. Floodwater built up on the southern side of the embankment before overtopping the track and washing away the ballast at 643.800 km. The culvert at 643.849 km and numerous other culverts along the Mid North Coast rail network had been identified as far back as 1995, as susceptible to overtopping leading to an increased risk of track washing away.
The driver of 4BM4 observed water in and around the rail corridor after passing Glenreagh but continued close to track speed (between 60-70 km/h) towards Nana Glen. On exiting a right-hand bend, train 4BM4 derailed at a washaway at 643.800 km.
Although ARTC had procedures in place for monitoring and responding to extreme weather events, the process had significant limitations. The mechanism (email) for alerting operational personnel required to respond to amber alerts did not ensure that alerts were always identified or actioned in a timely manner. Furthermore, the actions specified for amber and red alerts were insufficient to respond to escalating rainfall and flooding events, both forecast and actual.
It was also found that ARTC could not reliably determine the risk of flooding along the Telarah to Acacia Ridge corridor or the risks associated with inadequate capacity cross drainage systems.While remote weather monitoring stations were being installed, ARTC had not undertaken formal assessments to determine the need for these stations or the locations where they should be installed to detect extreme weather events that could affect the integrity of its rail infrastructure.
In addition, the weather alerts issued by the EWN did not reliably meet the requirements of ARTC’s extreme weather monitoring procedure or the service agreement under which the information was provided. This likely impacted the expectations of ARTC users who relied on these warnings to inform their response.
What has been done as a result
The following proactive safety actions have been communicated by ARTC as being completed, in progress or planned:
Installed an additional 20 remote weather stations along the Telarah to Acacia Ridge corridor, with plans to install an additional 50 remote weather stations and 500 stream flow monitors across their network in the next two years.
Developed and implemented a work instruction for the management of flooding and special locations. Introduced an enterprise-wide special locations register (to capture infrastructure such as non‑standard culverts) which is maintained through their asset management system.
In December 2022, ARTC released a safety bulletin which increased the rainfall and flooding alerts by one category (i.e. red alerts treated as black alerts) as a preventative measure based on the cumulated conditions impacting on the network including saturated catchments and the La Niña weather pattern.
Initially reviewed the contract with the Early Warning Network (EWN) to revise inconsistencies between the contract and extreme weather monitoring procedure (OPE‑PR‑014) and ensured that monitoring for the Hunter Valley commenced.
In December 2022, ARTC awarded a new weather monitoring contract to a different provider that incorporated additional requirements for monitoring rainfall near flooding special locations, and flood warnings for specific locations along their network. The service agreement acknowledged the safety-criticality of the information being provided and the contract was prepared in line with the requirements of ARTC procedure OPE-PR-014.
ARTC also engaged a consultant to undertake a hydrology review of their network. The hydrology review will identify the theoretical hydraulic capacity of all of ARTC culverts along the length of its network. This will determine what the culverts are capable of handling and then use a risk analysis to prioritise the locations for installation of monitors and consideration for upgrading to a greater hydraulic capacity. The hydrology review is being informed by the results of analysis by separate consultant on the effects of climate change focussing on the Brisbane to Albury corridor.
ARTC advised that they are undertaking a formal review of their extreme weather monitoring procedure. ARTC have initiated a project and engaged a consultant to develop a risk model to support real-time decision-making on operational responses to extreme wet weather events. The first stage of this project is to understand ARTC’s current operational responses to extreme wet weather events, and to assess the strengths, weaknesses and opportunities for improvement, having regard to contemporary wet weather incidents and current industry practice. Later project stages will involve the development of a risk model, along with the proposal of strategies to leverage the risk model to better inform ARTC’s management of extreme wet weather events.
ARTC also advised it had discussed with PN investigating improvements to the processes and actions required by train drivers and network controllers when flood water is observed in the corridor. PN advised they supported discussion between Rail Operators and the Network Operator with regards to the development of guidance material to support the CAN network rule. The ATSB welcomes the intention by ARTC and PN, however, has issued recommendations to both parties to develop guidance for train crew to respond to and report extreme wet weather events or floodwater in the rail corridor.
The EWN advised that they revised their rainfall alert system and added all ARTC’s rainfall monitoring gauges. The locations of ARTC’s flooding special locations were added to trigger amber alerts should rainfall exceed the defined threshold. Additionally, monitoring of rainfall depths for the Hunter Valley corridor had been setup and was being performed.
Safety message
Extreme weather events pose a significant risk to the rail network and are likely to increase in frequency and intensity into the future. These events can affect the integrity and exceed the design of rail infrastructure. Rail infrastructure managers must ensure that they have sufficient processes in place to actively identify, monitor and manage foreseeable risks in relation to extreme weather. These processes should be frequently reviewed to ensure that they remain adequate and appropriate.
Both rail infrastructure managers and rolling stock operators must also ensure that they provide guidance and operational procedures to enable consistent responses to conditions that may adversely affect the integrity of rail infrastructure and operational safety.
The occurrence
Events prior to the derailment
On 24 February 2021, freight train 4BM4 operated by Pacific National (PN) was scheduled to travel from Brisbane Freight Terminal (BFT), Queensland to Melbourne, Victoria. Train 4BM4 consisted of three locomotives (NR43, AN3 and NR39) and 37 wagons with a length of 1459 m and a total mass of 2422 t. The train was carrying dangerous goods located in the 20th, 23rd, 30th and 31st wagons.
At 1750,[1] driver A and driver B commenced their shift at the BFT and departed at approximately 1820. Driver A operated the train from BFT to Kyogle, New South Wales (NSW) where the drivers changed position, and driver B operated the train to Grafton. At Grafton the drivers changed positions again and driver A operated the train towards Nana Glen (Figure 1).
Figure 1: Main north coast rail line
Source: Geoscience Australia, annotated by OTSI
At 0112[2] on 25 February 2021, train 4BM4 travelling in the Up[3] direction diverted into the loop at Kungala (Figure 2) to allow freight train 3MB4 travelling in the Down direction to pass.
Train 3MB4 was travelling from Melbourne to Brisbane and was operated by PN. This service was followed by the XPT passenger service NT31 that was travelling to Brisbane.
Train 3MB4 passed 4BM4 at 0115 at Kungala and a roll-by inspection[4] was performed. The driver of 3MB4 recalled speaking with 4BM4 by radio and being advised their train was intact.
Following the passage of 3MB4, train 4BM4 departed Kungala at 0120 and operated at around 70 km/h towards Glenreagh. At 0129 train 4BM4 passed an XPT passenger service NT31 that was standing in the loop at Glenreagh (Figure 2). There was no communication between the two trains on passing.
Figure 2: Train crossing movements
The train paths of 3MB4 and NT31 are shown travelling in the Down direction (north) with 4BM4 travelling in the Up direction (south) with crossing movements shown at Kungala and Glenreagh. The upper image shows the trains passing at Kungala at 0115 and the lower shows the trains passing at 0129 at Glenreagh.
Source: ARTC, annotated by OTSI
At interview the driver of 3MB4 advised that they experienced extremely heavy rain from Coffs Harbour onwards and that the windscreen wipers were struggling to cope. They reported that as they reached the top of Red Hill (618.990 km) the rain became more intense and continued as they passed through Coramba and Nana Glen. They recalled noticing rainwater runoff in the corridor during the journey but did not see any floodwater at Nana Glen and continued.
The driver of NT31 reported at interview that between Coramba and Glenreagh the force of the rain was obstructing their visibility. They advised that they did not notice any water in the rail corridor when passing through Nana Glen.
There were no speed restrictions through the area and no track circuit faults at the time of the incident or in the previous 24 hours.
The derailment
Train 4BM4 passed through Glenreagh at 71 km/h and continued towards Nana Glen. The train’s speed decreased to 66 km/h by 646.010 km. It gradually decreased to 56 km/h by 644.510 km and was powering in throttle notch 5 to increase speed.
The driver of 4BM4 reported after passing Glenreagh they noticed water in the rail corridor and approaching the rail line. The front of train (FOT) footage showed water built up near the rail and water was visible primarily on the left-hand side of the track (Figure 3). On exiting a 300 m radius curve, the FOT footage showed a section of track that had been washed away a short distance ahead of the train at 643.800 km (Figure 4 and Figure 5).
Figure 3: Floodwater on approach to Nana Glen
The front of train footage showed an accumulation of water in the cess and on the formation primarily on the left-hand side about 130 m prior to the washaway.
Source: Pacific National, annotated by OTSI
Figure 4: Approaching the washaway
The image shows the front of train footage with the section of track immediately ahead of the locomotive.
Source: Pacific National, annotated by OTSI
Figure 5: Washaway
The image shows two sections washed away just prior to the train passing over. The floodwater was flowing from left to right.
Source: Pacific National, annotated by OTSI
At 0137 the train passed over the washaway while travelling at approximately 59 km/h. The lead locomotive dipped as it passed over the section of track and derailed, before bouncing out of the washaway and continuing. Both drivers reported they were thrown into the air when they passed over the washaway. Driver A was uninjured and driver B reported that at the time they felt some discomfort in their neck and shoulder.
The first locomotive derailed the first and sixth axles and the second locomotive did not derail. Both locomotives remained upright and came to a stand approximately 360 m from the point of derailment (Figure 6). The train separated between the second and third locomotive with the third locomotive (NR39) coming to rest on its left-hand side in the direction of travel (Figure 7). The first 10 wagons in the consist derailed and concertinaed to the left and right of the rail line as the train came to a stand. A number of wagons entered the floodwaters on the Orara River (northern side) and one container came to a rest in the field on the southern side near the high-water mark (Figure 6).
Figure 6: Derailment site
The image was captured by a helicopter at 1528 on 25 February almost 14 hours after the derailment. At 1530 the river height at Glenreagh (6.48 km north west of the derailment site) was recorded at 10.02 m with water from the Orara River visible on the northern side of the derailment site. The location of the washaway and resting place of the locomotives and wagons are shown. Cowans Creek ran towards the Orara River and drained through a culvert at 643.849 km. The grass was stained with a high-water mark visible where the water had receded.
Source: NSW Rural Fire Service, modified and annotated by OTSI
Figure 7: Third locomotive NR39 derailed
NR39 shown laying on the side with wagons derailed behind. The topography of the area can be seen to rise behind the derailment site.
Source: OTSI
Events post-derailment
Following the derailment driver B contacted the Australian Rail Track Corporation (ARTC) North Coast B Network Controller (NCO) to advise they had derailed. The NCO sought further information and arranged emergency services. Driver A left the lead locomotive to inspect the consist and reported that there were multiple wagons derailed. They were prevented from inspecting further due to floodwaters. The train crew could not confirm if the wagons containing the dangerous goods were involved in the derailment.
Driver B shut down the second locomotive (AN3). The crew left the lead locomotive running so they could keep the headlights on and make it easier to be spotted by emergency services. While inspecting the derailment site further, the crew identified the fuel tank on AN3 was leaking but were unable to block the leak.
A short time later driver B identified a small fire on the air compressor of lead locomotive (NR43) which the crew successfully extinguished with a portable fire extinguisher.
Extensive flooding in the local area prevented vehicle access to the derailment site for several hours. The train crew reported that police arrived approximately two hours following the derailment after walking in on foot. The police remained with them until maintenance personnel arrived around 0630 by road rail vehicle (RRV).
The train crew were evacuated from site shortly after and conveyed to Coramba before being transferred to Coffs Harbour, to be assessed by ambulance officers. The crew were then conveyed back to Brisbane by the operator arriving around 1400.
Post‑incident drug and alcohol testing was not conducted as it could not be performed within the required three-hour timeframe.
While AN3, the second locomotive did not derail, the fuel tank cracked during the derailment. Approximately 10,000 L of fuel was believed to have leaked due to a crack in the underside of the fuel tank. Fire and Rescue NSW responded to the site and plugged the damaged fuel tank to prevent further diesel leaking. Containment booms were also used to limit the spread of fuel and oil on the site.
There was damage to the track and embankment at the area of the washaway and derailment. There was scouring[5] on the downstream side of the embankment at the washaway due to the flow of water, with scouring to the toe of the embankment. A land slip had also affected a section of the embankment on the northern side between 643.820 and 643.900 km (Figure 8). The slip came within about 1 m of the end of the sleepers.
Figure 8: Post derailment site
The image shows the extent of the damage and scouring at the washaway as well as scouring to the embankment between 643.820 and 643.900 km. The inset image shows the proximity of the slip to the rail line and sleepers.
Source: Fire and Rescue NSW and Google Earth, modified and annotated by OTSI
The rail line was closed following the incident until the flood waters receded, rolling stock was removed and repairs could be completed. Approximately 140 m of track required repairs to the formation[6] and replacement of rail, sleepers, and ballast. Additionally, about 180 sleepers beyond the washaway also required replacement. The slip along the embankment and near the culvert outlet was repaired using geofabric and rock fill to stabilise the embankment. The rail line reopened with a temporary speed restriction at 2036 on 6 March 2021.
The cost of repairs to the site were estimated to be $1.07 million, and damage to rolling stock and recovery of the wagons estimated at $4.05 million. The cost of the rail line closure, damaged freight, emergency services response and environmental impact were not assessed but would likely have been significant.
Context
Involved parties
Australian Rail Track Corporation
The Australian Rail Track Corporation (ARTC) was a rail infrastructure manager (RIM) and managed 8500 km of rail network across five states (Figure 9). ARTC owned or leased most of the Defined Interstate Rail Network (DIRN).[7] ARTC divided the DIRN into the east‑west and north‑south corridors:
east-west – Cootamundra, NSW to Kalgoorlie, Western Australia (WA) and Crystal Brook, South Australia (SA) to Melbourne, Victoria.
north-south – Telarah, NSW to Acacia Ridge, QLD and Melbourne to Macarthur (near Sydney).
These corridors were further divided into separate corridors as shown in Figure 9.
Figure 9: ARTC rail network
Map showing the ARTC network and separate corridors.
Source: ARTC, modified and annotated by OTSI
Within NSW, the DIRN and Hunter Valley (HV) corridor were leased to ARTC in September 2004 under a 60‑year lease from the NSW Government.[8] The rail assets were transferred to ARTC from the State Rail Authority (SRA) and Rail Infrastructure Corporation (RIC).
In NSW, ARTC managed the rail network from:
Islington Junction to North Star/Camurra Junction
Goobang Junction to Gulgong via Dubbo and Merrygoen
Telarah to Loadstone
Macarthur to Albury
Parkes to Broken Hill
The Sydney Metropolitan Freight network (MFN).
Pacific National
Services 3MB4 and 4BM4 were both operated by Pacific National (PN) with their own train crew. PN was a privately owned rail freight operator with rail safety accreditation to operate across mainland Australia.
NSW Trains
Passenger service NT31 was operated by NSW Trains, an agency of Transport for NSW (TfNSW).[9] NSW Trains provided rail and coach services for regional NSW, including intercity, regional and interstate train services and a network of connecting coach services.
NSW Trains was a rolling stock operator with rail safety accreditation to operate in NSW, Victoria and Queensland. NSW Trains operated a fleet of electric and diesel hauled rolling stock.
Early Warning Network
Early Warning Network (EWN) was a provider of services relating to adverse weather events, alerts, forecasting, climate risk and other climate related issues. EWN were engaged by ARTC for their weather services through a contract.
Rail line information
Telarah to Acacia Ridge
The Telarah to Acacia Ridge (TAR) corridor was 776 km long and ran from 194.92 km at Telarah to 971.136 km at Acacia Ridge, Queensland. This rail line was also referred to as the main north or north coast rail line as it joined Sydney and Brisbane. The rail line was a standard gauge (1435 mm) single line with loops located along the line to allow passing movements for services travelling in opposite directions, or to allow faster services to pass freight services.
The derailment occurred at Nana Glen which was located about 25 km north-west of Coffs Harbour on the Mid North Coast of NSW.
The TAR corridor was susceptible to East Coast Lows (ECL)[10] which could produce gale force winds, and heavy rain leading to flash flooding and major river flooding. ECL could be difficult for forecasters to accurately predict where they would occur along the east coast and could intensify rapidly.
Coffs Harbour to Kungala
From Coffs Harbour the rail line ran in a north-westerly direction rising up Red Hill to Landrigans before it gradually descended towards Glenreagh. The track speed for freight services in the Up direction varied between 70-100 km/h and 70-125 km/h for passenger services. In the Down direction the speed for freight services was between 60-80 km/h and 75-110 km/h for passenger services.
The track speed for freight services between Glenreagh and Nana Glen was 70 km/h in both the Up and Down direction. The XPT was permitted to travel between 75‑95 km/h in that section and through the derailment site the track speed was 75 km/h.
Between Coramba and Glenreagh there were 18 level crossings with the first at 624.727 km and the last at 651.600 km just before the loop at Glenreagh. Only four of those crossings had active protection with the remaining fitted with passive stop signs.
Between Karangi (622.906 km) and Kungala (664.460 km) the rail line ran in close proximity to the Orara River and crossed a number of other rivers and creeks. The Orara River drained to the Clarence River at Grafton and was subject to flooding.[11]
Nana Glen
At Nana Glen there was a loop located at 641 km. The rail line passed over several creeks including Bucca Bucca and Cowans Creek that joined the Orara River. There were a number of curves and the rail line was built on a freestanding embankment at the derailment site. The rail was 60 kg/m and was fastened to concrete sleepers by heavy duty resilient clips. The ballast depth was approximately 300 mm below the sleepers. The subgrade material comprised of clay material from the adjacent cutting.
Train information
4BM4
Train 4BM4 was an interstate freight service operating from Brisbane Freight Terminal (BFT) to Melbourne Freight Terminal. The train consisted of three locomotives, NR43 (leading), AN3 and NR39 and 37 wagons. The train had a total mass of 2422 t and a length of 1459 m.
The wagons were a mixture of containerised freight on single flat top wagons, 5 packs[12] and one well wagon (2 pack). As the train passed over the washaway, the leading portion of the train derailed and divided between the second and third locomotive. When the train separated, the brake pipe was broken, resulting in an emergency brake application along the length of the train.
The following locomotives and wagons derailed or were damaged in the derailment:
NR43 – derailed the first and sixth axle and remained upright
AN3 – did not derail, fuel tank damaged and leaked approximately 10,000 L diesel, remained upright
NR39 – derailed and on rolled on left-hand side, no fuel leaks
1st wagon – RCQY00715K
2nd wagon – RQHY07037G
3rd wagon – RRAY07253E
4th wagon – RQJW60037P
5th wagon – RRQY07306A
6th wagon – RQSY34446R
7th wagon – NQGY34470Q
8th wagon – RQFY00111K
9th wagon – RQSY34427K
10th wagon – RQJY60000U.
The three locomotives were repaired following the derailment. The 10 wagons derailed were made up of two 5-packs and eight wagons (18 platforms in total). Nine out of the 10 wagons that derailed were damaged beyond repair and scrapped. The cost associated with the damaged rolling stock and recovery of the wagons was estimated at $4.05 million.
There were dangerous goods[13] on the consist but they did not derail and were undamaged. The dangerous goods were located in the following wagons:
20th wagon – RRQY08343 – 23,000 L resin solution, flammable – UN No. 1866
23rd wagon – RQSY35042 – 40,000 L environmentally hazardous substance,[14] liquid, N.O.S.[15] (wastewater) in two tanks – UN No. 3082
30th wagon – RQFY00126 – 23,000 L resin solution, flammable – UN No. 1866
31st wagon – RQPW60078F
12,000 kg aerosols, 288 kg paint or paint related material and 224 L paint or paint related material – UN No. 1263.
40 kg flammable liquid, N.O.S (ink) – UN No. 1993.
The combination and quantity of the dangerous goods posed a risk to the train crew and surrounding environment if they had derailed.
Fuel tanks
During the derailment, the fuel tank on AN3 was damaged, causing an 18 mm crack on the underside of the tank. The contents of the 10,800 L tank leaked from the crack. There was other damage to the tank although no other leaks.
The fuel tank on NR39 had several impacts but remained intact during the derailment and when the locomotive rolled over.
The fuel tanks on both NR39 and AN3 were sealed, excluding the vents (breather pipes). The vents had a ball within the valve designed to close the valve in the event of a roll over. This design prevented the fuel from NR39 spilling into the floodwaters and reduced the hazards on site.
NT31
Train NT31 was the scheduled 1441 Sydney to Brisbane XPT passenger service operated by NSW Trains. The train consisted of two locomotives (power cars) and six trailer cars.[16] At the time of passing through Nana Glen at 0109, there were six train crew and 36 passengers on board. The train crew consisted of one driver and five on-board staff.
3MB4
Train 3MB4 was an interstate freight service operating from Melbourne Freight Terminal to Brisbane Freight Terminal. The train consisted of three locomotives and 37 wagons. The train had a total mass of 3327.91 t and a length of 1477.80 m.
There were dangerous goods on two wagons consisting of 27,000 kg of sulphur (molten), 1400 kg aerosols, 96 kg of flammable liquid (corrosive) and 250 kg of paint or paint related material.
Train crew information
4BM4 – Driver A
Driver A of 4BM4 was an experienced rail worker and appropriately qualified train driver. They were employed with PN for over nine years and had worked as a train driver for about six years.
Driver A commenced duty at 1750 on 24 February 2021, at their home depot in Brisbane, to operate train 4BM4 from Brisbane, Queensland to Taree, NSW with a co-driver (driver B). Driver A recalled being fit for duty and feeling refreshed after rostered days off. They were familiar with and experienced on the route, conducting one to two trips per week over the prior 15 months, with most duties at night. They had driven with driver B previously, although they were not the co‑driver they would normally drive with.
The train departed the Brisbane Freight Terminal (BFT) at 1820. Driver A stated that the journey was uneventful, up until the period immediately preceding the derailment. They reported that they were not provided with any adverse weather advice, before commencing or during the trip.
Driver A and driver B conducted changeovers in driving duty during the trip. Driver A operated from Brisbane to Kyogle, NSW before handing over to driver B, who operated from Kyogle to Grafton. Driver A resumed driving from Grafton up to the occurrence location.
The train stopped at Kungala, NSW to cross train 3MB4, then continued once clear. The train also crossed train NT31 at Glenreagh, standing in the loop.
Driver A reported that after departing Kungala, there was heavy rain and large amounts of water located around the rail corridor.
Driver A also reported observing rainwater building up in the rail corridor from Glenreagh, and that it was raining steadily. They recalled water mainly on the left side of the train (in the direction of travel), between the ballast and wall of the cutting, with the depth increasing towards the rail head, about 1-1.5 km before the derailment. The water appeared to be stationary, not fast moving.
Driver A reported that they had the locomotive’s headlights on but that it was dark, with reduced visibility due to rain. They stated that if they had observed water over the rail head, they would have stopped the train. At the time, they considered that the depth and position of the water, in proximity to the rail, did not meet the criteria for reporting to the Network Controller (NC).
Driver A recalled thinking that it was safe to proceed given two other trains (3MB4 and an XPT) had already travelled through the area, and the drivers of the other services and the NC had not advised them of any issues.
Driver A later reported that on approaching Nana Glen, they noticed the water on the side of the track encroaching towards the rail, with no water visible on the rail. It was dark with heavy rain. Driver A operated the train at around 65 km/h through that section where the maximum permissible speed was 70 km/h in that location.
Driver A stated that as the train travelled around the right curve (direction of travel) at Nana Glen, there appeared to be no indication of any track issues. Suddenly, the lead locomotive dipped and dropped about half a metre into water, before bouncing back up, jolting the drivers around in their seats. Driver A applied the emergency brake but believed the consist may have already separated and waited for the train to stop. The train crew then checked with one another that they were uninjured. Driver A was uninjured. Driver B reported feeling a twinge in their shoulder at the time.
Driver B notified network control while driver A left the cabin with a torch to survey the situation. Driver A observed that a locomotive was on its side, and wagons derailed to the left and right of the track. They were surrounded by water on the left and a significant drop in the topography on the right. A short time after the derailment, the train crew observed a small fire on the lead locomotive. Driver B extinguished the fire using a portable fire extinguisher.
The train crew were evacuated from the site about 0700 on 25 February 2021 by a road rail vehicle. They were then transferred to Coffs Harbour where they were checked by ambulance officers. The train crew were then transferred back to Brisbane by PN.
Driver A roster
In the 14-day period prior to and including the occurrence shift, driver A worked six shifts. They were rostered off from duty for 60 hours before commencing duty on 24 February 2021 (Table 1). Their roster was in accordance with the operator’s fatigue management requirements and there were no identified issues.
Table 1: Actual duty times for driver A for 14-day period
Date
Duty start
Duty end
Duty time
Time free (of duty) before next shift
11 February 2021
1400
2149
7 hours 49 minutes
12 February 2021
Rostered off
13 February 2021
Rostered off
14 February 2021
Rostered off
15 February 2021
Rostered off
16 February 2021
Rostered off
17 February 2021
2015
0900
11 hours 45 minutes
12 hrs 15 minutes
18 February 2021
2115
0702
9 hours 47 minutes
13 hrs 58 minutes
19 February 2021
2300
0600
7 hours
40 hours
20 February 2021
Rostered off
21 February 2021
2200
0549
7 hours 49 minutes
60 hours 1 minute
22 February 2021
Rostered off
23 February 2021
Rostered off
24 February 2021
1750
1340
19 hours 50 minutes
4BM4 – Driver B
The co-driver of 4BM4 (driver B) was an experienced rail worker and appropriately qualified train driver. They were employed with PN for over nine years as a train driver.
Driver B commenced duty at 1750 on 24 February 2021, at their home depot in Brisbane, to operate as a co-driver for train 4BM4 from Brisbane, Queensland to Taree, NSW with driver A. Driver B recalled being fit for duty at sign on for the occurrence shift. They were familiar and experienced on the route, having operated the service during night shift only.
Driver B reported that the departure of 4BM4 was delayed on 24 February 2021, due to a loading issue. They then proceeded as normal, with driving duties shared with driver A.
Driver B recalled that it had been raining during the trip, with the rainfall intensifying after leaving Grafton. Approaching Nana Glen, they experienced heavy rainfall, which resulted in reduced visibility from the cab. At that time, the locomotive air conditioner malfunctioned, and condensation was building up on the cab windscreen. They reported they did not see any water on the rail.
Driver B reported that during the occurrence trip, there were no weather alerts or condition affecting the network (CAN)[17] issued.
Driver B recalled that they approached the occurrence site at about 65 km/h. The lead locomotive dropped down then bounced out of a dip, up to the other side. Driver B sustained minor musculoskeletal injuries and items in the cab were dislodged. Driver B reported that they did not observe the track washout before the occurrence.
After coming to a stop, Driver B recalled driver A went out with a torch to assess the situation. Driver B notified network control of the derailment and advised that further information would be provided when available. Driver A then advised driver B, via radio, that the lead and second locomotive were separated from the rest of the train, with the third locomotive on its side and the wagons derailed behind.
Driver B continued with further calls to initiate the internal emergency response. The train crew then surveyed the site with torches, to determine if there were any immediate hazards to be managed. The second locomotive was shut down and the lead locomotive left running, to provide lighting from the headlights and visual reference for emergency responders.
The train crew returned to the lead locomotive and secured it. Driver B isolated the electrically driven compressor, which was making significant noise. About 20 minutes later, driver B identified that the compressor’s low oil light was illuminated and went to visually inspect it. The compressor was on fire. Driver B went back to the cab to alert driver A and get the portable fire extinguisher. Driver B then successfully extinguished the fire.
The train crew then identified a fuel spill from the second locomotive, which they reported to emergency services, who were in contact to determine the crew’s location and whether there were any dangerous goods on the train.
The first emergency responders were police officers on foot. Other emergency services and responders arrived after.
Driver B roster
In the 14-day period prior to and including the occurrence shift, driver B worked three night shifts. They were rostered off from duty for over 17 hours before commencing duty on 24 February 2021 (Table 2). Their roster was in accordance with the operator’s fatigue management requirements and there were no identified issues.
Table 2: Actual duty times for driver B for 14-day period
Date
Duty start
Duty end
Duty time
Time free (of duty)
11 February 2021
2245
0840
9 hrs 55 minutes
12 February 2021
Rostered off
13 February 2021
Rostered off
14 February 2021
Rostered off
15 February 2021
Sick certificate
16 February 2021
Sick certificate
17 February 2021
Rostered off
18 February 2021
Rostered off
19 February 2021
Rostered off
20 February 2021
Rostered off
21 February 2021
Rostered off
22 February 2021
Rostered off
23 February 2021
1400
0022
10 hours 22 minutes
17 hours 28 minutes
24 February 2021
1750
1340
19 hours 50 minutes
NT31 – Driver C
The driver of NT31 (driver C) was an appropriately qualified regional passenger train driver for NSW Trains, based at Grafton for about 4 years at the time of the occurrence. They had worked as a passenger train driver for about 12 years and employed with NSW Trains as a driver for over 5 years. They were experienced and familiar with the route operated by NT31 between Taree and Grafton, for both day and night operations.
On 24 February 2021, driver C was called out to operate passenger service NT31 from Taree, in place of a rostered duty out of Grafton. They recalled being fit for duty. Driver C was transferred via taxi from their home to Taree Station. NT31’s scheduled departure from Taree was at 2008. However, that night the service was delayed by about 80 minutes. Driver C relieved the outgoing driver of NT31 at Taree and continued operating the service to Grafton.
Driver C reported that the weather conditions on the night of the occurrence from Coramba to Glenreagh, were the worst that they had encountered in their driving career. They reported at interview that visibility was significantly reduced ahead, with no visibility to the left or right of the cab, due to intense rainfall. Driver C stated that they did not observe any water in the vicinity of the tracks, noting that the visibility was limited. The train’s headlights provided reduced lighting of the track ahead, with the cab windscreen wipers operating at maximum setting. Driver C recalled that they operated through that section from about 0058 to 0120 on 25 February 2021. They had driven a service through the same section two days earlier and there were no noticeable differences between services.
From Coffs Harbour to the distant signal at Glenreagh, NT31 had all green signals. At Glenreagh, the signal indicated that NT31 was to enter the crossing loop. A freight train passed NT31, which Driver C later learned was 4BM4.
NT31 then proceeded towards Kungala, where the NCO informed driver C that there was a derailment at Nana Glen due to the line washing away. The NCO advised they would hold NT31 at the home signal (42-3) at Kungala, so that a freight service could enter the loop. After being held at Kungala for about 30 minutes, NT31 proceeded to Grafton Station where driver C was relieved of duty as planned.
Driver C recalled that they did not make or receive any communication from other train drivers during that duty. They reported that typically, there would only be communications with the freight train crews if they observed any issues with the freight train, or to assist by advising the drivers when their train was clear in a crossing situation.
Driver C reported that they had not received any weather advice or alerts either prior to commencing duty on 24 February, or during that shift. They reported that they were surprised there was no weather alert issued by network control. Driver C was personally aware of a period of ongoing rainfall of about two weeks prior to the occurrence date, as they lived in the region. In their experience, they had previously observed floodwater in the Nana Glen showgrounds area (near 640.500 km) where the loop was located, when there was heavy rainfall. They had not seen water encroach the rail corridor and could not see the area on the night due to the conditions.
Driver C stated that if they observed floodwater in the rail corridor near the rail, they would advise network control. They considered that water approaching the rail head would constitute a CAN.
3MB4 – Driver D
The driver of 3MB4 (driver D) was an appropriately qualified train driver with over 17 years’ experience as a freight train driver operating between Melbourne and Brisbane, with the majority of their duties conducted at night.
Train 3MB4 was the last freight train to pass through the occurrence site about 43 minutes before the derailment of 4BM4.
Driver D recalled that while operating 3MB4, the weather slowly deteriorated as the train travelled north. There was no weather advice or alerts received from network control. Driver D also recalled that they received communication from network control about a requirement to maintain 3MB4 ahead of a following XPT service. Driver D reported operating on schedule and driving in accordance with the speed boards.
After departing Coffs Harbour, the rainfall became more intense approaching the top of the range, at Red Hill. Train 3MB4 continued through Coramba towards Nana Glen. Around Nana Glen, there was heavy rainfall, with the maximum speed of the locomotive cab windscreen wipers unable to keep the windows clear, due to the intensity of the rain. They travelled through Nana Glen at 0053 on 25 February, and through the incident site at about 0054. Driver D stated that they did not experience any abnormal line conditions at that time but noted that there was very heavy rainfall.
Driver D reported that they observed water starting to accumulate near the rail line through the section, but not near the level of the rail head. Due to the heavy rain, there were small streams of water runoff in the cess.[18] However, driver D also reported that the amount of rainwater water runoff was not as extensive as they had observed in the past, when operating through the same area. Trees adjacent to the line were hanging low and heavy from the rain, with 3MB4 hitting some low branches as the train travelled through. Driver D noted that the conditions were comparable to those resulting from a thunderstorm and not unusual.
After travelling through Nana Glen, train 3MB4 passed the stationary 4BM4 in the loop at Kungala at 0115. Driver D recalled they communicated with 4BM4, that their train was intact, and they could see the end of train marker as they passed, which was normal procedure. There was no other communication between the drivers. Driver D reported that radio coverage to communicate with other trains was limited once they were more than a train length apart. If they needed to communicate further, it would need to be via network control.
Driver D continued and they reported being unaware of the derailment at Nana Glen until their arrival in Brisbane.
Driver D reported at interview that trains would be stopped when water was above the rail head as water would then contact the locomotive traction motors, leading to faults. If water was running across the track, driver D would notify network control. Conditions on 25 February 2021 experienced by driver D did not meet these criteria. Driver D recalled that they had experienced such conditions previously, operating in a southerly direction on that line at Red Hill, towards Sydney, and had notified network control on that occasion.
Environment and weather
Forecast
The EWN provided the daily TAR corridor forecast to ARTC at 0809 on 24 February with the three-day look ahead, the daily forecast stated:
North of Coffs Harbour, isolated to scattered showers and isolated storms will be possible about the corridor over the course of today as an upper trough combines with onshore winds. Activity will mostly remain weak however there is the low chance of some severe storms occurring between Coffs Harbour and Grafton, and the moderate chance of severe activity north of Grafton to Acacia Ridge. Mostly the risk of damaging wind gusts is expected though the impacts of this will remain quite localised with rainfall rates remaining below the thresholds of concern. Storm activity is unlikely to occur today south of Coffs Harbour with showers expected across the remainder of the corridor.
Tomorrow will see showers and storms develop across the entire corridor as a broad area of instability extends along the eastern coastline of NSW. Expect the highest risk of severe storms to occur between Newcastle and Kempsey though rainfall rates will remain below the thresholds of concern. North of Kempsey, activity will tend more isolated with showers with activity largely remaining weak (though the risk of damaging winds cannot be ruled out).
Associated with the forecast was a colour coded geographical breakdown of the TAR corridor between Woodville Junction, NSW and Acacia Ridge, Queensland. The section NSW/QLD Border and Acacia Ridge were coded as amber[19] with a moderate risk (30-50 per cent) of severe storms. Between Coffs Harbour and Grafton it noted low risk (10-30 per cent) of severe storms and they were colour coded as green (Figure 10). The forecast for the three days (Thursday to Saturday) ahead were also colour coded as green.
Figure 10: EWN TAR corridor forecast 24 February 2021
Colour coded geographical breakdown of the TAR corridor with rainfall recorded in the previous 24 hours and predicted rainfall for the next 24 hours. Nana Glen was between Coffs Harbour and Grafton.
Source: Early Warning Network
The Bureau of Meteorology (BoM) provided two forecasts on 24 February 2021 for the Mid North Coast district, with the first issued at 0515 stating:
Weather Situation - A low pressure system lies near New Zealand, while a ridge of high pressure across Victoria extends an onshore flow across the eastern districts of New South Wales. A trough lies across inland New South Wales, and is likely to promote unsettled weather in many central and eastern districts over the coming days.
Forecast for the rest of Wednesday 24 February - Cloudy. High (80%) chance of showers. The chance of a thunderstorm during this afternoon and evening.
The second forecast was issued at 1630 and contained the same notes for the weather situation and the forecast noted ‘High (80%) chance of showers. The chance of a thunderstorm’.
NSW Trains utilised the BoM forecasts as well as any warnings from various rail network operators to inform their network services weather alerts. On 24 February these alerts were communicated at 0830 and 1800 to their operational personnel and were posted at train crewing sign on areas.
PN advised that their personnel within Integrated Planning Services (IPS) monitored the BoM website during extreme weather events. There was also a dedicated television screen that displayed the weather radar to monitor weather events. PN advised that use of some of this information was reliant on receiving weather alerts or reports of issues from either trains or network operators. In relation to defining if it was safe to operate trains, PN relied on ARTC as the rail infrastructure manager (RIM) to monitor and respond to extreme weather events.
Weather warnings and alerts
At 2152 on 24 February 2021 the BoM issued the following severe thunderstorm warning:
Severe thunderstorms are likely to produce damaging winds, large hailstones and heavy rainfall that may lead to flash flooding[20] over the next several hours in the North West Slopes and Plains and parts of the Hunter, Central Tablelands, Central West Slopes and Plains and Northern Tablelands districts. Locations which may be affected include Armidale, Tamworth, Gunnedah, Moree, Narrabri and Coonabarabran.
Severe thunderstorms are likely to produce heavy rainfall that may lead to flash flooding over the next several hours in parts of the Northern Rivers, Mid North Coast and Northern Tablelands districts. Locations which may be affected include Coutts Crossing, Nymboida and Glenreagh.
This warning was identified by the EWN as relevant and EWN communicated the alert to ARTC at 2159. The warning stated that heavy rainfall may lead to flash flooding and listed Glenreagh as an area that may be affected. The initial warning was communicated by the EWN to ARTC as an amber alert within 7 minutes of the BoM issuing the warning. The BoM threat map as depicted in the warning did not appear to show that the rail line would be affected by the weather event (Figure 11).
Figure 11: BoM severe thunderstorm warning 2152 and 2208 24 February 2021
The threat map for the severe thunderstorm warning issued at 2152 is shown on the left with the warning issued at 2208 on the right. In the later, the threat map warning area changed with the warning area now stretching to the coastline.
Source: Bureau of Meteorology, annotated by OTSI
The EWN advised that they reviewed each alert generated by the BoM and communicated those assessed as genuine alerts to ARTC. If the BoM issued more than one warning for the same weather event, the warnings would only be communicated to ARTC if there was an escalation of the event or significant time had passed between the warnings.
The BoM issued three further severe thunderstorm warnings prior to the derailment (Table 3). The subsequent warnings were not assessed as an escalation by the EWN, and ARTC received no further warnings.
The second alert issued by the BoM at 2208 provided similar information to the first alert however the threat map showed the warning area over a larger portion of the north coast and could impact the rail line (Figure 11). The warning escalated the threat to ‘Severe thunderstorms are likely to produce intense[21] rainfall that may lead to dangerous and life-threatening flash flooding’.
Table 3: Severe weather warnings
Date
Time
Warning Description
Comments
24 February 2021
2152
Severe thunderstorms are likely to produce heavy rainfall that may lead to flash flooding over the next several hours in parts of the Northern Rivers, Mid North Coast and Northern Tablelands districts.
Amber alert issued to ARTC at 2159.
24 February 2021
2208
Severe thunderstorms are likely to produce intense rainfall that may lead to dangerous and life-threatening flash flooding, damaging winds and large hailstones in the warning area over the next several hours.
No alert issued by EWN.
Escalation of threat level by BoM. Change of threat map area.
25 February 2021
0114
Severe thunderstorms are likely to produce heavy rainfall that may lead to flash flooding over the next several hours in parts of the Northern Rivers, Mid North Coast and Northern Tablelands districts.
No alert issued by EWN.
25 February 2021
0132
Severe thunderstorms are likely to produce heavy rainfall that may lead to flash flooding over the next several hours in parts of the Northern Rivers, Mid North Coast and Northern Tablelands districts.
No alert issued by EWN.
Prior to the derailment, the BoM issued two flood warnings for the Orara River at Glenreagh. The first warning was issued at 0003 on 25 February with minor flooding occurring at Glenreagh and flooding predicted to reach 5.8 m by 0200. The second warning was issued at 0034 with minor flooding occurring and flooding predicted to reach 7.4 m by 0200. Following the derailment, there were eight other flood warnings issued for the Orara River at Glenreagh and Coutts Creek (33 km north-west of the derailment site) between 0200 and 2045.
Weather observations
Rainfall
The BoM weather station at Nana Glen[22] recorded 310 mm of rain to 0900 on 25 February 2021. This was the highest recorded rainfall for this station. This station provided readings on a 24‑hour period but it was likely that the 310 mm fell over a much shorter duration.
Weather stations surrounding the area recorded between 80 mm and 216 mm while Coffs Harbour recorded 63 mm in 24 hours (Figure 12).
Figure 12: Record rainfall at 0900 on 25 February 2021 and river height monitoring locations
The figure shows the north coast rail line in orange with the recorded rainfall for weather stations around the derailment site. The Orara River is shown in red with the locations for the river gauges at Glenreagh, Orange Grove and Karinga marked in orange.
Source: Google Earth, annotated by OTSI
River heights
Between 0000 and 2000 on 24 February 2021 the Orara River at Glenreagh[23] rose from 1.83 m to 2.75 m, the height then rapidly rose to 8.59 m by 0130 on 25 February 2021. Rises in river height were also recorded at Orange Grove and Karangi[24] in the same period (Table 4 and Figure 12). The Orara River at Glenreagh peaked at 10.59 m after the derailment at 0930 on 25 February before beginning to recede. The river height would likely have peaked earlier at Nana Glen as the gauge at Glenreagh was approximately 8.8 km further downstream.
Table 4: Orara River heights 24 - 25 February
Date
Time
Glenreagh
Orange Grove
Karinga
24 February 2021
0000
1.83 m
2.46 m
1.43 m
2000
2.75 m
2.47 m
1.46 m
2100
2.96 m
2.64 m
1.54 m
2200
3.55 m
3.04 m
1.68 m
2300
5.30 m
3.57 m
1.88 m
25 February 2021
0000
6.98 m
3.79 m
2.13 m
0100
8.15 m
3.81 m
2.29 m
0130
8.59 m
3.97 m
2.35 m
0200
8.94 m
3.86 m
2.39 m
Source: Bureau of Meteorology
There was no river height monitoring for the Bucca Bucca Creek which joined the Orara River about 2 km south-west of the derailment site. Lower Bucca recorded 216 mm of rain which would have very likely contributed to the rapid rise in the river height at Glenreagh (Figure 12).
Radar
The BoM Grafton weather radar[25] was the primary weather radar for the North-East of NSW, with a southern range to Kempsey. It was located at the NSW Agriculture Research Station, Grafton, about 57 km north of the occurrence site.
The Grafton weather radar indicated consistent light to moderate precipitation (up to 35 mm/h) in the Nana Glen region, from 1710 on 24 February. The rainfall intensity increased in the area from about 2030, up to 50 mm/h, then up to 80 mm/h at 0050 on 25 February. A rain band of heavy intensity remained in the area and was present at the time of the derailment.
Simulations undertaken by the EWN for the rainfall accumulations based on the Grafton radar in the 6-hours to 0115 on 25 February, suggested rainfall of between 200‑300 mm may have fallen near the derailment site (Figure 13). Rainfall exceeding 300 mm may have fallen further east which was likely outside the catchment for Cowans Creek.
Figure 13: 6-hour rainfall accumulations to 0115 on 25 February 2021
Simulated radar rainfall accumulations shown with the colours depicting the accumulated rainfall depth on the map with the scale at the bottom. The approximate location of the derailment site is depicted.
Source: EWN, modified and annotated by OTSI
Climate conditions
In the months leading up to the event, the BoM declared a La Niña[26] weather pattern (Climate Drivers Update - 29 September 2020). In December 2020, the BoM predicted (Climate Drivers Update – 22 December 2020) that there would be above average rainfall January to March for most of the eastern third of Australia, which included the TAR corridor.
The effects of the La Niña as noted in the Australian Institute for Disaster Resilience (AIDR) Major Incidents Report 2020-2021 were that:
The 2020–21 La Niña increased the likelihood of rain bearing weather patterns over eastern Australia and it reduced evaporation due to increased cloudiness and reduced temperatures. These conditions resulted in an increase in soil moisture during the spring and summer, meaning any heavy rainfall on the wet catchments saw less water soaked up by the ground and a tendency for rivers to respond more quickly and reach higher levels compared to dry catchments.[27]
Actual rainfall preceding months
Between 1 December 2020 and 28 February 2021 large sections of the north coast of NSW recorded rainfall between 600 mm and 1400 mm (Figure 14). In the same period the weather station at Nana Glen recorded a total of 1530.8 mm, with 581.6 mm in December, 358.2 mm in January and 591 mm in February. Large sections of the north coast recorded rainfall either very much above average or highest on record between December to February (Figure 15).
Figure 14: New South Wales total rainfall (mm) 1 December 2020 to 28 February 2021
Rainfall map for New South Wales with the approximate location of Coffs Harbour shown.
Source: Bureau of Meteorology, annotated by OTSI
Figure 15: New South Wales rainfall decile ranges 1 December 2020 to 28 February 2021
Rainfall decile map for New South Wales with the approximate location of Coffs Harbour shown.
Source: Bureau of Meteorology, annotated by OTSI
Climate change
The North Coast Climate change snapshot predicted that in both the near future (2020 to 2039) and far future (2060 to 2079) that the NSW North Coast was likely to experience:
increases in maximum temperature and number of hot days above 35°C
decreased rainfall in winter but increased rainfall in autumn and spring
summer rainfall was projected to decrease in the near future but increase in the far future.[28]
The existing TAR rail corridor was designed prior to considerations of climate change and in some areas the infrastructure did not meet modern standards.
In relation to rainfall, it was noted in the State of the Climate 2020 report that:
Observations show that there has been an increase in the intensity of heavy rainfall events in Australia. The intensity of short-duration (hourly) extreme rainfall events has increased by around 10 per cent or more in some regions and in recent decades, with larger increases typically observed in the north of the country. Short-duration extreme rainfall events are often associated with flash flooding, and so these changes in intensity bring increased risk to communities.
…
As the climate warms, heavy rainfall events are expected to continue to become more intense. A warmer atmosphere can hold more water vapour than a cooler atmosphere, and this relationship alone can increase moisture in the atmosphere by 7 per cent per degree of global warming. This can cause an increased likelihood of heavy rainfall events. Increased atmospheric moisture can also provide more energy for some processes that generate extreme rainfall events, which further increases the likelihood of heavy rainfall due to global warming.[29]
The impact of more intense rainfall on existing infrastructure will likely be significant. Particularly in areas where the design of drainage systems does not meet modern standards or where the rail corridor is in close proximity to rivers and creeks. However, the influence of these changes may not be felt immediately.
Network control
Network Control Centre
The train control function for the DIRN within NSW was performed by the Australian Rail Track Corporation (ARTC) Network Control Centre South (NCCS) located at Junee, NSW.
The NCCS controlled the interstate operations on the DIRN between Acacia Ridge to Telarah, Macarthur to Melbourne, and Cootamundra to Broken Hill (Figure 9). The NCCS also controlled the Sydney Metropolitan Freight network.
The incident occurred within jurisdiction of the NCCS Coast B Board (known as the North Coast B Board), from Kempsey Signal 30-1 at 503.863 km to Acacia Ridge (Queensland) AR 1 Signal at 971.136 km. This section was a single line and method of train control was Rail Vehicle Detection (RVD).[30]
The NCCS was managed by the Service Delivery Manager (SDM), who reported to the General Manager Operations.
The Train Transit Manager (TTM), who reported to the SDM, was responsible for management of the transit of trains across the interstate network, in accordance with customer access contracts. The TTM role provided supervision of the NCCS, including the Network Controller (NCO) roles.
The role of the NCO was to oversee the day-to-day operational control of safeworking systems, including:
guide plans and manage the movement of trains over the ARTC network
control and recording of train performance
movement of trains and track vehicles over prescribed sections of ARTC’s railway network in accordance with ARTC Safe Working Rules and Procedures.
The Hunter Valley corridor was managed by the Network Control Centre North (NCCN) located at Broadmeadow, NSW. The NCCN was responsible for monitoring and responding to extreme weather events for the Hunter Valley corridor. The control centre operated in a similar manner although had some different titles due to the nature of the coal network operations.
Train Transit Manager
The TTM on duty, at the time of the occurrence, had over 17 years of experience in that role. They were trained and certified as competent.
The TTM was rostered on the night shift, from 2200 on 24 February to 0600 the following morning. They reported that they were fit for duty and did not recall feeling fatigued.
The TTM recalled at interview that they were aware that the north coast region was flooding but could not exactly recall how they were aware other than information from previous shifts. They stated that weather information was available by accessing weather radar data via the BoM website but that they relied on the EWN alerting system in operation in the NCCS.
The TTM reported that the computer displaying Bureau of Meteorology (BoM) weather radar images, in the foyer area of the NCCS, was generally for local area information and interest, and was not a designated weather information source.
The TTM stated that their role involved active monitoring and problem resolution within the NCCS, with minimal time in the separate TTM office, where their computer was located. In the event that an EWN amber alert was issued, it was transmitted to them via email. However, they would need to be at their computer to receive it. The NCOs would receive an amber alert email to their workstations if it was emailed to them by the TTM, but these may not be read. The TTM could not recall if an amber alert was issued or current at the time of the occurrence.
The TTM reported that on the night shift, they may convene a meeting at midnight with the NCOs, dependant on what was happening. The process was not documented and consisted of verbal discussion and briefing on relevant issues, such as weather and/or upcoming work/possessions. The TTM could not recall if a meeting was conducted with the NCOs during the occurrence shift.
Train Transit Manager roster
In the 14-day period prior to and including the occurrence shift, the TTM worked 13 shifts, with a single rostered calendar day free from any duty.
The TTM’s worked roster for that period contained two shift changes that were backwards rotating, with a minimum period away from duty of eight hours, between shifts (Table 5).
Table 5: Actual duty times for TTM for 14-day period (local times)
Date
Duty start
Duty end
Duty time
Time free (of duty) before next shift
11 February 2021
0600
1400
8 hours
16 hours
12 February 2021
0600
1400
8 hours
16 hours
13 February 2021
0600
1400
8 hours
16 hours
14 February 2021
0600
1400
8 hours
32 hours
15 February 2021
2200
0600
8 hours
16 hours
16 February 2021
2200
0600
8 hours
8 hours
17 February 2021
1400
2200
8 hours
8 hours
18 February 2021
0600
1400
8 hours
16 hours
19 February 2021
0600
1400
8 hours
56 hours
20 February 2021
Rostered off
21 February 2021
2200
0600
8 hours
8 hours
22 February 2021
1400
2200
8 hours
24 hours
23 February 2021
2200
0600
8 hours
16 hours
24 February 2021
2200
0600
8 hours
Network Controller
The NCO on duty on the North Coast B Board, at the time of the occurrence, had over 24 years of experience in NCO roles and had worked at ARTC’s NCCS since its commencement in 2004. They were trained and certified competent.
The NCO was rostered on the night shift, from 2300 on 24 February to 0700 the following morning. They reported that they were fit for duty.
On sign on, the NCO was assigned the North Coast B Board for the duration of the shift. At the time of the occurrence, the NCO had been on duty for about 2.5 hours. They reported that their plans were already in place and were in the execution phase. They stated that they did not feel fatigued.
The NCO reported that up until the derailment, the shift was uneventful, with normal traffic and workload patterns. The NCO recalled that there were no active weather warnings for the area, that they were aware of, in the period prior to the occurrence.
The NCO reported that weather information was available in the NCCS via a computer displaying the Bureau of Meteorology (BoM) weather radar images. The NCOs were also able to access the BoM weather radar images at their workstations. In addition, the Train Transit Manager (TTM) received weather alerts via email, which they would then verbally communicate to the relevant NCOs.
The NCO reported that ‘stand-up meetings’ were conducted around the period each NCO shift started. The TTM would brief the NCOs on several items, including any network issues and weather alerts. The NCO could not recall if a meeting was conducted at the commencement of the involved shift but considered that it would have occurred.
While the NCO later reported that they had received a briefing from the Train Transit Manager, ARTC had no record of any briefings completed on 24 or 25 February 2021.
The NCO recalled that their first communications with the involved train crew was a radio call from the driver reporting the derailment and location. The NCO reported that after checking on the welfare of the crew, the emergency response commenced. During the response, heavy rain in the area continued delaying the arrival of personnel to the derailment site.
The NCO reported feeling surprised when the derailment was reported, as the XPT had traversed the same section of track about 30 minutes earlier, without incident or report of a CAN, such as water near the rail head.
Network Controller roster
In the 14-day period prior to and including the occurrence shift, the NCO worked 11 shifts. In the seven-day period, from 11-18 February 2021 inclusive, the NCO worked 68 hours. The operator’s guidelines were for a maximum of 60 hours worked in seven days.
The NCO’s worked roster contained several shift changes that were backwards rotating, with a minimum period away from duty of eight hours, between shifts (Table 6).
Table 6: Actual duty times for NCO for 14-day period (local times)
Date
Duty start
Duty end
Duty time
Time free (of duty) before next shift
11 February 2021
Rostered off
12 February 2021
0800
1600
8 hours
15 hours
13 February 2021
0700
1500
8 hours
12 hours
14 February 2021
0300
1500
12 hours
12 hours
15 February 2021
0300
1500
12 hours
32 hours
16 February 2021
2300
0700
8 hours
8 hours
17 February 2021
1500
2300
8 hours
16 hours
18 February 2021
1500
0300
12 hours
58 hours
19 February 2021
Rostered off
20 February 2021
Rostered off
21 February 2021
1500
2300
8 hours
8 hours
22 February 2021
0700
1500
8 hours
32 hours
23 February 2021
2300
0700
8 hours
16 hours
24 February 2021
2300
0700
8 hours
Network Control Centre South fatigue management
The operator’s WHS-WI-423 Fatigue Work Instruction[31] outlined their processes to manage risks associated with fatigue. It applied to all ARTC employees, including those employed in the NCCS. A Fatigue Monitoring System was not in operation at the NCCS.
Section 2.2 Schedule work hours documented ‘hours of work guidelines’ including:
Maximum hours in 7 days 60 hours
Maximum hours in 14 days 108 hours
Maximum hours in 28 days 192 hours
Forward rotation of shifts Day -> Afternoon / Night -> Night.
The document stated that ‘forward rotation of shift means a pattern of shifts that rotate from day to afternoon to night’.
The documented stated that ‘should work be required outside of these guidelines, the likely level of additional risk(s) involved will be assessed and appropriate risk control measures identified’.
The method/process for assessing additional risks and identifying appropriate risk control measures was not defined, nor what control measures should be applied.
ARTC reported that where the shift cycles did not conform with the guidelines in WHS-HI-423, the ‘NCCS ensures the minimum specified time between shifts (8hrs) is applied and confirms at the start of every shift, as part of the sign on process, that each Network Controller is fit for work and not suffering the effects of fatigue’.
Track standards
Flooding
ARTC’s Code of Practice Section 10 Flooding[32] detailed how flooding was to be managed. The standard was divided into three sections including design and ratings, construction and maintenance, and inspection and assessments.
Design and ratings
The design of waterways[33] and drainage systems was to be in accordance with Australian Standard AS 5100,[34] Waterways Design Manual, Australian Rainfall and Runoff and Australian standards as applicable. ARTC advised that the applicable standards were AS 7637 and RTS 3433 for new railways on greenfield sites.[35]
These standards did not apply to existing infrastructure and there was no requirement to assess existing drainage systems against these standards. Additionally, this standard did not define the design flood events (flood immunity)[36] or the floodwater level relative to the track for a flood event.
Construction and Maintenance
This detailed the requirements for cleaning waterways and that care must be taken when performing maintenance to avoid undermining embankments or retaining structures.
Inspections and assessments
A register of special locations was to be established and maintained for sections of track that had been prone to flooding and flood damage.
Scheduled inspections were required, with patrol inspection performed weekly and general inspection performed annually. The persons conducting the patrol inspection were to keep a look out for scouring, blockage or partial blockages of waterways and indications of flood damage such as overtopping[37] and culvert or drain damage. The general inspection required additional inspection for scouring around culverts and structures, erosion to waterways and blockages or loss of slope for track drains and waterways.
Unscheduled inspections were required at flooding special locations or in response to suspected defects found during a patrol inspection, automatic rainfall monitoring or reported heavy rain and flooding. These inspections were required to check the integrity of the waterway and drainage systems and monitor the flood conditions until the risk had passed.
At the time of the derailment in 2021, there were no flooding special locations registers for NSW. The Corridor Manager (CM) reported that due to the flood prone nature of the TAR corridor they considered the entire corridor as a flooding special location.
Structures
Code of Practice Section 9 – Structures[38] was applicable to the design of new railways, road and rail bridges, culverts, and other significant structures on greenfield sites.
In relation to bridges and culverts, the design requirements for waterway infrastructure were dependant on the discharge of water through the structure. Major undertrack structures with discharges greater than 50 m3/sec were to be designed to 1% Annual Exceedance Probability (AEP),[39] structures with discharge less than this were considered minor and were designed to 2% AEP or 50 Annual Recurrence Interval (ARI).[40]
New bridges were required to be designed to have a flood immunity and serviceability limit of 100 ARI or 1% AEP as required by AS 5100.[41] ARTC reported that most existing bridges were built for 100 ARI flood events, although there was no requirement to confirm their flood immunity or serviceability limit.
Replacements of existing culverts was not addressed as part of the standard and there was no requirement to assess an existing structure against this standard.
Structures – culverts
The maintenance requirements for culverts were detailed in Structures Inspection ETE-09-01.[42]Culverts less than 500 mm were maintained and inspected by the civil maintenance team with larger culverts required to be inspected by qualified structural inspectors.
Culverts required a visual inspection every two years, with an inspection latitude of 10 per cent (+73 days). The purpose of the inspections was to assess the physical condition of the structure and that the structure was safe for operational purposes (continued safe use).
The inspection criteria included checking the culvert for subsidence, cracking, blockage and deformation or broken / separated joints. The inlets and outlets were also checked for cracking of the headwalls and wingwalls, scouring under the apron and heaving of the floor (Figure 16). Defects were defined based on the size or type of defect with a corresponding defect category. Depending on the defect size, the response ranged from monitoring to immediately stopping trains. Culverts that were blocked by more than 20 per cent were required to be reported, while less than 20 per cent could be monitored.
Figure 16: Culvert endwall structure
Source: Australian Rainfall and Runnoff, modified and annotated OTSI.
Technical Maintenance Plan
The maintenance requirements for ARTC’s infrastructure were detailed within their Civil Technical Maintenance Plan ETE-00-03.[43] This document detailed what items required inspection and the frequency of the inspection. The maintenance inspection requirements for structures were defined with the Code of Practice Section 9 – Structures and Structures Inspection ETE‑09-01 as above.
Track patrols were conducted weekly from a road rail vehicle along the corridor. The inspection scope was a general visual inspection and included but was not limited to inspection of the rail, sleepers, ballast, track geometry, earthworks, structures, drainage, signage, and level crossings.
While track patrols were conducted regularly, the inspections were limited to the detection of large or obvious defects on or near to the rail line.
More detailed general inspections were carried out annually, with those relevant to the occurrence below:
Earthworks – Inspection of embankments, cuttings, and geotechnical sites. Inspections included checking for slippage, slumping or heaving, scouring and erosion of track and embankments.
Flooding – inspection of waterways, surface drains (cess, top and toe), cess drainage pipes less than 500 mm.
Maintenance records
The maintenance records provided showed that the section of track had been inspected in accordance with ARTC’s TMP requirements with the most recent relevant inspections detailed at Table 7.
Review of the recent inspections against rainfall at Nana Glen and river height at Glenreagh on the day of the inspection and in the week prior, did not identify any periods of heavy rainfall that would have led to flooding at Nana Glen. During the most recent inspections, it was likely that there were no obvious signs of water accumulating at the culvert at 643.849 km.
Table 7: Recent maintenance inspections
Date
Task
Track kilometrage
21/09/2018
Visual Inspection of Large Culvert
643.849 km
25/11/2019
Visual Inspection of Small Culvert
643.481 km
25/11/2019
Visual Inspection of Small Culvert
644.015 km
27/02/2020
General Inspection of Earthworks - Geotechnical Sites
486.827 km to 739.620 km
05/05/2020
General Inspection of Earthworks - Embankments and Cuttings
486.827 km to 739.620 km
05/05/2020
Drainage - General Inspection
486.827 km to 739.620 km
24/06/2020
General Inspection of Waterways and Drainage Systems
486.827 km to 739.620 km
19/08/2020
General Inspection of Ballast
486.827 km to 739.620 km
30/08/2020
Visual Inspection of Large Culvert
643.849 km
19/01/2021
Detailed Inspection of Track Geometry - Recording Car
486.827 km to 739.620 km
11/02/2021
Front of train inspection
486.827 km to 739.620 km
16/02/2021 and 17/02/2021
Track Patrol
486.827 km to 739.620 km
23/02/2021 and 24/02/2021
Track Patrol
486.827 km to 739.620 km
Track drainage
Derailment site
The track at Nana Glen was in place when ARTC took over the management of the rail corridor in 2004. While details for the locations of culverts was recorded in their asset maintenance system, ARTC did not have any detailed design specifications or drawings for the culverts.
In the immediate vicinity of the derailment site at 643.800 km there were two culverts passing through the embankment with: a large culvert at 643.849 km and a small culvert at 644.015 km. The embankment at the site had a maximum height of between 5-10 m high. There was also a small culvert at 643.481 km that was not within the embankment but any flows that bypassed the culvert would have flowed towards the large culvert at 643.849 km.
The culvert at 643.849 km was a steel reinforced concrete pipe and was 24 m long with a nominal diameter of 2 m (2020 mm x 1970 mm). The inlet elevation to the invert [44] was 63.66 m and the outlet invert was at 63.45 m (Figure 17).[45] The culvert invert was nominally 9.8 m below the top of the rail, which was at an elevation of 73.398 m. The inlet and outlet of the culvert had concrete headwalls and wingwalls (Figure 18 and Figure 19). The slope of the culvert was approximately 1.7 in 200 (1.7 m in 200 m). There were no records for when this culvert was installed.
For further details relating to culverts see Appendix C – Culvert concepts.
The culvert at 643.849 km was inspected on 30 August 2020 and on 21 September 2018.
Photographs taken on 28 February and 1 March 2021 showed that some debris had collected around the inlet and some small branches were near the inlet. These photographs showed that the culvert about the water line was not blocked. Some of the debris would likely have moved as the water levels receded.
Figure 17: Track drainage
Drawing depicting a cross section of the embankment at the derailment site through the culvert at 643.849 km. The elevations for the culvert inverts and rail heights are also noted. Not to scale. The elevations were in reference to the Australian Height Datum.
Source: OTSI
Figure 18: Culvert inlet
The inlet of the culvert at 643.849 km is shown with the headwall and wingwalls. Debris was present near the inlet with some small branches laying across the channel as well as collected above the culvert.
Source: ARTC, modified and annotated by OTSI
Figure 19: Culvert outlet
The outlet of the culvert at 643.849 km is shown with the headwall and wingwalls. The culvert was visibly clear above the waterline and the branches visible at the inlet could be seen.
Source: ARTC, modified and annotated by OTSI
The large culvert at 643.849 km permitted Cowans Creek to flow through the embankment towards the Orara River. Cowans Creek ran in a northerly direction and was fed by runoff water coming from the south-east and flows coming off the steep escarpment which rises to approximately 300 m above the derailment site (Figure 20). The approximate catchment[46] size for Cowans Creek required to discharge through the culvert at 643.849 km was approximately 400‑450 ha or 4-4.5 km2.
There were two other smaller culverts located on either side of the derailment site (643.481 km and 644.015 km) that allowed water to flow towards the Orara River. These culverts were not fed from Cowans Creek.
The working plan noted that the embankment in the vicinity of the derailment had previously been washed away. It contained several handwritten notes marked as from April 1962:
643.68 to 643.71 km - scour 8-feet [2.43 m] deep
643.71 to 643.84 km - embankment completely washed away 14-feet [4.26 m] deep
643.84 to 643.91 km - scour 10-feet [3.04 m] deep.
The working plan also contained a record dated from 1938 that suggested the embankment at 643.600 km had been totally washed away. It was not clear what was the exact date of this or the source of the information.
Public records suggested that a railway embankment at Nana Glen had been washed away during the 1950 floods, however, the location was not noted.[47]
Figure 20: Topographical map and Cowans Creek
The grid is 1 km and contour lines are in 10 m increments. The approximate catchment area is highlighted in the red dashed line and was approximately 400-450 ha or 4-4.5km2.The path of 4BM4 is also marked in orange showing the approach to the derailment site.
Source: NSW Sixmaps, modified and annotated by OTSI
There were several rivers and creeks that joined the Orara River near Nana Glen including the Bucca Bucca Creek approximately 2 km south-west of the derailment site, and the Coldwater Creek approximately 800 m from the derailment site (Figure 20). A flood study undertaken for the Coffs Harbour Council for the Orara River noted:
The Orara River and Bucca [Bucca] Creek confluence downstream of the village of Nana Glen, and receive inflows from a number of significant tributaries, as follows:
Urumbillum River, Mirum Creek and Fridays Creek, discharging to the Orara River in Upper Orara;
Wongiwomble Creek discharging to the Orara River near Karangi;
Nana [Creek] and Coldwater Creek discharging to the Orara River near Nana Glen; and
Kings [Creek] and Finberg Creek discharging to Bucca [Bucca] Creek upstream of Nana Glen.[48]
It was likely that these creeks contributed to the rapid rise in Orara River height recorded at Glenreagh on 24-25 February 2021.
Culvert assessment study
In 1995, the then infrastructure manager SRA commissioned the North Coast Line Culvert Assessment.[49] This assessment was for culverts between Nana Glen (640.000 km) to Glenreagh (651.600 km) and Gurranang (727.900 km) to Lawrence Road (734.100 km).
The assessment consisted of developing a system to analyse the culvert capacity and assess the risk of failures, and to develop a prioritisation method for remedial works.
A total of 52 culverts were assessed as part of the study with the results summarised as:
15 of 52 culverts listed with capacities less than once in 20 year event [20 ARI]
washout or ash apparent in 5 of the 15 culverts and occurs with embankments heights between 2 to 10 metres
34 of 54 culverts have capacity greater than 50 years
4 culverts needed immediate attention.
The risk of overtopping was assessed as flooding exceeding the nominated freeboard[50] height under the designed rainfall conditions. The total freeboard height utilised for the assessment was 0.8 m below the top of the rail. The embankments were assessed for overtopping and ranked from those most likely to suffer from overtopping to the least likely due to the culvert capacity. The culvert nearest to the derailment site (643.800 km) at 643.849 km was ranked as 14th with the culvert at 643.481 km ranked 18th.
The culvert at 643.849 km was assessed at risk of overtopping the embankment for events of between 1 in 10 and 1 in 20 ARI. Evidence of ash[51] and previous washaways were also found at that location.
There were no records available for what actions, if any, were taken by SRA at the time of the study to address the issues. ARTC had records of the report and the information was recorded in their geotechnical sites database.
Geotechnical database
ARTC geotechnical database for Coramba (634.290 km) to Glenreagh (654.160 km), contained summary notes for the geotechnical sites along the corridor. In this section there were 121 geotechnical sites.
The geotechnical site where the derailment occurred was between 643.400 and 644.050 km. The site was described as:
Freestanding embankment. RH->LH [right-hand to left-hand]. Part of the embankment widened on the Downside during LX [level crossing] widening. Ash visible at 643.600 km and road base visible under track from 634.7 km to 634.75 km (was probably emergency fill).
Small culvert at 643.481 km, large culvert at 643.849 km and small culvert at 644.015 km.
Sag point in vertical curve ~643.8 km, with track grade rising for ~800 m City and Country sides.
The waterway area is too small. Hydrological study shows culverts at 643.481 km and 643.849 km are under capacity. Refer to report by Paterson Consultants June 1995.
Additional observations for this site were recorded as:
29/09/2005 - This problem is primarily to do with hydrology and no significant geotechnical problem was observed.
10/05/2016 - No change to site conditions. TP [Track Patrol] report no problems. Hydrology problem. Increase waterway.
There was a geotechnical risk ranking against those observations and the status was listed as inactive. There were no other records available from ARTC for this site. The hard copy records from the previous infrastructure maintainer were missing for this specific geotechnical site.
The database contained references to at least seven culverts identified as undersize through this section. These included those assessed as part of the culvert assessment study as well as others identified as having problems during rainfall and flooding of the Orara River.
ARTC were unable detail how these flood risks were assessed or provide copies of risk assessments associated with the identified risks.
ARTC weather monitoring
Weather monitoring and response
East-west corridor
ARTC’s extreme weather monitoring procedure (OPP-01-05)[52] was originally developed for the east-west corridor[53] in 2014. The procedure detailed the roles and responsibilities for the various network control and corridor personnel. The procedure required an Extreme Weather Group (EWG) made up of appropriately qualified ARTC staff to make decisions in relation to forecast extreme weather events[54] for amber, red and black forecasts (Table 8). The EWG consisted of representatives with sufficient seniority and expertise to formulate the organisation’s response. This group could assess and consider if the alert needed to be elevated to a red or black alert or downgraded to an amber or red alert.
A risk matrix was developed as part of the procedure which broke down weather events into rainfall, flooding and wind. The risk rankings were colour coded from green, amber, red and black alerts to denote the level of perceived risk (Table 8). The description for each level escalated from no threats to severe network disruptions or damage. The risk matrix detailed the severity of the weather for the corresponding alert level (Table 9).
The BoM provided rainfall data that could be used to assess rainfall Intensity, Frequency and Duration (IFD)[55] for an area. The IFD information, in conjunction with the Australian Rainfall and Runoff (ARR) 1987 guideline, was utilised to determine the design rainfall Average Recurrence Interval (ARI) for the ARTC east-west rail corridor.
The east-west corridor was broken into six different geographical areas[56] and an ARI rainfall depth for the durations of 1 hour, 6 hours, 24 hours and 72 hours were developed. ARTC advised that the thresholds of 20 ARI and 50 ARI for the red and black levels was to account for culverts that could be susceptible to rainfall events that exceed those limits. The intent was that should rainfall exceed a 20 ARI a red alert would be generated and if the 50 ARI was exceeded a black alert would be generated.
Stream flow monitoring gauges were also fitted to some culverts and configured to generate a black alert if flow was detected.
The procedure contained responses for rainfall / flooding, and wind that were colour coded and detailed the actions to be taken by the responsible party. Weather events classified as black were the most extreme risk, requiring all operations in the affected area to cease.
The procedure detailed the mechanism for communicating alerts and warnings to the nominated recipients as:
Green – Email
Amber – Email
Red – Email and text message (SMS message)
Black – Email and text message (SMS message).
Additional updates were also available to ARTC personnel for amber, red and black alerts if they wished to contact the EWN.
Defined Interstate Rail Network and Hunter Valley
In August 2017, ARTC expanded their extreme weather monitoring procedure to include their entire rail network with the procedure re-named OPE-PR-014.[57] Between 2017 and 2019 the extreme weather monitoring procedure was revised on three occasions. The version current at the time of the derailment was last updated in June 2019.[58] The risk matrix, threat level and mechanism for communicating forecasts, alerts and warnings was unchanged from the original procedure with most changes being clarification of roles or titles.
The EWG role was changed from the original procedure (OPP-01-05) from reviewing amber forecasts to one that was only required to review and assess forecast red and black alerts for rainfall / flooding as well as black alerts for wind. The purpose of the group, which was unchanged according to the revised procedure, was to determine the ARTC’s response to forecast extreme weather events.
The revised procedure (OPE-PR-014) divided the network into the Defined Interstate Rail Network (DIRN) and the Hunter Valley (HV) network. The roles and responsibilities were updated to reflect the differences in network control personnel for these two networks. The DIRN was divided into four corridors and the HV was listed as a standalone corridor. Each of the corridors was further divided into a total of 50 different geographic areas with a corresponding ARI threshold for each of five sections. The corridors consisted of the following sections:
Kalgoorlie to Cootamundra (KFC) – 6 geographic areas
Melbourne to Crystal Brook (MAC) – 10 geographic areas
North Corridor (Sydney to Brisbane) – 9 geographic areas
South Corridor (Melbourne to Sydney) – 10 geographic areas
Hunter Valley – 15 geographic areas.
Refer to Appendix B – ARTC and EWN rainfall monitoring areas for further details.
Under the revised procedure, responses to rainfall / flooding and wind were listed separately for the DIRN and HV but had similar responses for both networks for those alerts. The full details of the response required by ARTC personnel to the different alerts is contained in Appendix A – OPE-PR-014 response tables.
In response to the amber alert issued by the EWN at 2159 on 24 February, the TTM was required under the procedure (OPE-PR-014) to ‘advise operators and other network users[59] of the current alert level’ and to ‘ensure operators are advised’. The process of advising operators and network users required the TTM to send an email to a distribution list that would advise both internal users (NCOs, asset management and support functions personnel) and externals users (rolling stock operators and customer management centre) of the alert and its level.
As per the ARTC procedure, the Corridor Manager (CM), Service Delivery Manager (SDM) and Area Manager (AM) were also required to respond to amber alerts as outlined below and as per Table 14 the:
Corridor Manager was required to consider more frequent track inspections including inspection of culverts and water levels, and to make arrangements, if needed, to enable inspections after downpours or reports of high water.
Service Delivery Manager was required to advise customers of potential network disruptions due to an extreme weather event.
Area Manager was required to provide local input, collect information from maintenance crew, develop a local response plan and hold toolbox meetings as required.
At the time of the alert, the CM, SDM and AM were not working but had on-call personnel available who would have also received the alerts.
At interview the CM reported that they were woken by a message for the amber alert, but as on‑call personnel were available, they did not feel that it warranted further action by them. The CM advised that in any event, as it was an amber alert, they would typically wait for further alerts before responding as it was only a forecast alert. If further alerts were received detailing how much rain had fallen then that would have been the trigger for them to respond.
The CM reported that if it was a red alert or larger weather events were forecast, they would have considered mobilising personnel to inspect the network or position personnel at locations of known risk.
On the night of 24-25 February there were no track patrols or inspections prior to the derailment.
Rainfall thresholds
The ARI for the North Corridor between Border Tunnel (876.5 km) and Woodville Junction (595 km) is shown in Table 10. The ARI was for the overall corridor section rather than a specific location within the section.
Table 10: Border Tunnel to Woodville Junction ARI
In 2016, the BoM provided a new data set for the assessment of design rainfall IFD.[60] This replaced the 1987 dataset that was used by ARTC to determine the ARI thresholds for their procedure (OPE-PR-014). The actual ARI for the derailment site was higher than the thresholds specified for the Border Tunnel to Woodville Junction section. The design rainfall depths for Nana Glen are shown in Table 11 with the ARI and corresponding AEP.
Table 11: Nana Glen IFD design rainfall ARI and AEP
Weather monitoring service
At the commencement of the original weather monitoring service, ARTC engaged the EWN through a purchase order with standard terms and conditions. In April 2017 and prior to ARTC formally expanding their extreme weather monitoring procedure, they requested a quote from the EWN to include weather monitoring for the north-south and Hunter Valley (HV) corridors. The EWN provided the quote based on the service they were already providing for the east-west corridor with the inclusion of the new network areas. The quote was accepted in May 2017 and formalised the services the EWN were providing into a consultancy service agreement (CSA) contract (CA-SA-05445-00).
Monitoring of ARI rainfall depths required the EWN to identify weather stations within 50 km of the east-west and HV corridors, and 25 km of the north-south that would be used. Most stations were from the BoM and those were configured within the EWN monitoring software to trigger at the ARI thresholds. ARTC had also installed some remote weather monitoring stations with most along the east-west corridor to provide additional coverage. At the time of the occurrence, the nearest working ARTC weather station was at Roto, NSW, approximately 786 km from the derailment site.
The EWN had configured the weather stations for the east-west corridor as part of the weather monitoring for ARTC’s original procedure (OPP-01-05) and there were no changes to those stations. However, they needed to identify and configure the additional weather stations required for the expansion of the weather monitoring procedure (OPE-PR-014) to include the north-south and HV corridors and the revised 2017 contract. To allow the EWN to complete this work they required the following information from ARTC:
location of the rail corridor
appropriate corridor boundary (25 km and 50 km either side of the corridor)
threat matrix and rainfall depths for the sections
distribution list detailing who was to receive the alerts.
In May 2017, ARTC provided this information to the EWN. The EWN later advised ARTC that the new weather monitoring services would commence on 10 June 2017. The EWN commenced the weather monitoring for the DIRN and HV before ARTC’s revised weather monitoring procedure (OPE-PR-014) had been completed. It was completed in August 2017.
While not detailed within ARTC’s procedure, ARTC had requested EWN to provide a phone call service for all red and black alerts. The phone call was to consist of an automated message to the relevant network control centre to advise of a red or black alert.
When the inclusion of phone call notifications for red and black alerts was requested in November 2018, ARTC discovered that EWN had not implemented weather monitoring for the entire HV corridor. Instead, weather monitoring had only been set up in 2017 for Woodville Junction and Telarah.
Following this discovery, the EWN provided a new proposal that included weather monitoring for the entire HV corridor. The CSA was amended on 18 December 2018 to reflect this change. The EWN advised ARTC that forecasting for the entire HV corridor was set up and would commence on 2 January 2019.
The CSA was amended on three occasions (in December 2018, September 2019 and June 2020) to either extend the term of the contract or add additional culvert flow monitoring equipment along the east-west corridor.
In 2020, ARTC requested a revised service proposal from EWN which was accepted and became CA-SA-06312-00.[61] At the time of the occurrence, the services EWN provided under the CSA included:
Rainfall alerts – Colour coded (red and black) alerts utilising BoM and ARTC rainfall data to trigger when ARI thresholds were exceeded. Alerts to trigger for durations of 30 minutes, 1 hour, 6 hours and 24 hours.
Culvert (flow monitor) alerts – Colour coded alert generated if flow was registered in the culvert (amber), height reached the top of the culvert (red) or bottom of the sleepers (black). There were 36 culverts fitted with flow monitoring equipment along the east-west corridor.
Weather and bushfire alerts – There were six different alerts that the EWN provided that included:
Bushfire Watch & Act
Bushfire emergency warnings
Severe thunderstorm warning only if destructive winds in the headline
Severe weather warnings if destructive winds and/or heavy rain in the headline
Tropical cyclone watches and warnings
Tsunami warnings.
Daily brief and three-day forecast – Forecast for the DIRN and HV compiled by a qualified meteorologist for rainfall, temperature, wind and fire bans. The forecast was required to be sent by 0900 each morning.
The weather and bushfire alerts were required to be communicated to ARTC within 6-8 minutes of the BoM issuing an alert. The EWN issued an amber alert at 2159 on 24 February. It was communicated within seven minutes and there were no other alerts communicated to ARTC.
ARTC weather monitoring equipment
Automatic Rainfall Monitoring
ARTC had an engineering standard Automatic Rainfall Monitoring[62] that was applicable to NSW only. This standard detailed the requirements for determining the need for automatic rainfall monitoring (ARM) through to installation and commissioning. The standard was divided in to four stages including:
Initial assessment – Determine if a particular site or general areas were at increased risk of rainfall and identify areas where existing risk controls (track patrol, speed restriction) would not be effective.
Investigation – Geotechnical and hydrological studies to assess the rainfall conditions and risk at the site. Additional requirement to assess the risk characteristics including traffic density and type, stopping distance as well as system characteristics (train control and response times).
Detailed design – Review all information and develop the detailed design including thresholds and alert levels to be communicated to network control.
Purchasing, installation and commissioning – Approval to purchase and install once detailed design was complete. Commissioning and testing of equipment and alerts to network control.
The standard also contained a specific note that reassessment must be conducted at intervals of two years or less due to the likelihood of changing conditions over time.
Remote weather monitoring
In the week prior to the derailment, a remote weather monitoring station[63] had been installed at Nana Glen at 639.500 km. This station was approximately 3.7 km from the derailment site (643.800 km) but was not operating and commissioned at the time. A remote weather station had also been installed at Craven (290.724 km) on the TAR corridor and while working had not been commissioned. The station at Craven was approximately 250 km from Nana Glen. A further 12 remote weather stations were planned to be installed along the TAR corridor at:
Oakhampton 198.613 km
Dungog 245.747 km
Mt George 342.141 km
Wauchope 454.740 km
Kempsey 503.634 km
Koolkhan 706.321 km
Camira Creek 756.439 km
Wiangaree 846.210 km
Loadstone 864.210 km
Glenapp 888.550 km
Tamrookum 905.430 km
Greenbank 955.259 km.
At interview the CM indicated that the original intent of installing remote weather monitoring stations was to monitor temperature for track stability during hot weather. This was first considered in 2014, however, did not progress at the time. Further information provided by ARTC suggested that the locations for the 14 remote weather stations were selected in 2018/2019. Once installed and commissioned, the data from the weather stations was available to the EWN for their weather monitoring service.
Risk register
In March 2020, the installation of remote weather monitoring stations was listed as a proposed control within ARTC’s risk register which detailed the risk of Inclement weather (including flooding). The proposed treatment date for implementation of that control was listed as 30 June 2020.
Approximately two months after the derailment, the risk register was revised on 26 April 2021 with the risk re-named Infrastructure loss or degradation due to a weather event. A new treatment date of 30 June 2021 was listed for the installation of remote weather monitoring equipment as this work had not been yet completed. The description of the control was:
Placing remote weather stations at critical points where there is no information at the BoM. The information is web based and log-ins will be supplied to the EWN group to enhance their service.
The other controls listed within the risk register included ARTC’s weather monitoring procedure (OPE-PR-014) and the EWN service.
There were no stream flow detectors along the TAR corridor at the time of the occurrence and they were not considered within the risk register.
Network rules and procedures
Condition affecting the network
Network rule ANGE 206 Reporting and Responding to a Condition Affecting the Network (CAN)[64] detailed the requirements for reporting and responding to unsafe conditions affecting or potentially affecting the network. The requirements for reporting were:
Conditions that can or do affect the safety of rail operations in the ARTC NSW Network must be reported promptly to the Network Control Officer responsible for the affected portions of track.
The Network Control Officer must record the information on the Train Control Graph or where used in the Train Register Book.
If necessary, the competent worker[65] reporting the CAN was required to prevent rail traffic approaching the area by applying track protection. The NCO was required to communicate the CAN to other NCOs as well as operators’ representatives. As necessary, the NCO was also required to:
arrange to warn rail traffic crews of rail traffic approaching the affected portions of track
arrange to prevent rail traffic from approaching the affected portions of track, and apply blocking facilities
arrange for the 1500V supply to be isolated in accordance with Rule ANGE 228 Unplanned removal of 1500V supply
ask Maintenance Representatives to investigate.
Within rail vehicle detection (RVD) areas, a written CAN was required to warn rail traffic when the CAN related to the following conditions:
CAN block working is introduced
faulty or potentially faulty level crossings have been reported
level crossing warning equipment has been deactivated
rail traffic must be restrained where blocking facilities cannot be applied
speed restrictions during hot weather have been reported
temporary speed restrictions have been reported and no signs erected.
If possible, the NCO was to arrange for a competent worker to give a CAN form to the rail traffic crew prior to entering the affected portion of track. Where it was not possible, the NCO was to dictate the contents of the CAN to the rail traffic crew. Where a CAN did not relate to the above conditions, the NCO was permitted to give spoken (verbal) CAN warnings to rail traffic crews.
Rail traffic crew were required to acknowledge and comply with CAN warnings.
The NCO was required to continue warning rail traffic crew until the CAN no longer existed or the crew were warned by other means (such as signage). If maintenance representatives were asked to attend and investigate, the CAN was only able to be removed once the track had been certified as safe for rail traffic.
Responsibility of rail traffic crew
Rail traffic operating through the ARTC controlled network were required to comply with ARTC network rules and procedures. The responsibilities for rail traffic crew operating on ARTC’s network was prescribed in ANGE 232 Responsibilities of Rail Traffic Crews (Train Crews and Track Vehicle Crews).[66] Train crews were responsible for the safe operation of rail traffic and the safety of other crew and passengers. Train crew were also required to be qualified to operate the rail traffic and in the systems of safeworking for the area. This rule was applicable to both Pacific National and NSW Trains.
In addition to this, NSW Trains had their own procedure NTTWP 100 Responsibility of Train Crew[67] detailing the responsibilities of their train crew (drivers, guards and passenger service supervisors). The responsibilities of the train driver included, but were not limited to:
immediately inform Network Control Officers or any other relevant employees of any incident, problem or defect relating to trains, signalling, track or overhead wiring, or any other problem affecting or likely to affect train services.
operate the train in accordance with the requirements contained in the Professional Driving Guide[68]
be alert for and obey all fixed signal indications, Railway Track Signals and handsignals
if visibility is affected, slow the train to maintain safety
keep the train under control so that it can be stopped by applying the automatic air brake, if required
apply appropriate train management techniques for customer comfort…
The Rail Industry Safety and Standards Board (RISSB) network rule ANRP 2027 Responsibilities of Rail Traffic Crews[69] provided additional details for rail traffic vigilance. Rail traffic crews must:
observe the track in the direction of travel, and
be prepared to stop or reduce rail traffic speed if required, and
reduce rail traffic speed if it is considered that the conditions prevent safe operation at normal speed, and
pay particular attention when:
visibility is impaired for any reason, or
when approaching:
a crossing or passing location, or
signals, indicators and signs or
level crossings…
This rule was not mandatory for rail infrastructure managers but provided industry recommended best practice.
Australian and international rules – wet weather and flooding
Heavy rainfall and flooding have led to washaways and derailments across Australia and overseas (see Similar occurrences). In response to previous flooding, washaways and derailments, Queensland Rail (QR) and Aurizon both released safety alerts or guidance in 2016 which were similar in their wording. The Aurizon safety alert stated:[70]
Train Traffic Crew must immediately STOP and report to the Network Control Officer:
water on the formation and near the ballast
any potential track or formation deficiencies
if the track formation and / or supporting ballast cannot be seen
any signs of washouts or scouring on the side of the ballast or formation…
The diagram shown in Figure 21 was included in the safety alert to assist with identifying the sleepers, ballast and formation.
Figure 21: ATSB investigation RO-2018-007 - Except from Aurizon safety alert showing difference between ballast and formation
Source: Aurizon
In 2017, Aurizon issued a guide for Operations of rail traffic in adverse weather. The guide was to assist train crews operating in adverse weather. In relation to wet weather and where visibility was affected it stated:[71]
When it is necessary to operate rail traffic during fog, heavy rain, unexpected storms and similar circumstances where there is reduced visibility, RTC [rail traffic crew] are to take appropriate steps to protect their safety, the safety of the rail traffic and the track infrastructure by driving to the conditions. RTC should assess the situation and regulate the speed of the rail traffic in accordance with the conditions, and advise the NCO and LRC [live run coordinator] of their intended action, i.e. they are proceeding at reduced speed because of low visibility.
If operation of rail traffic in heavy rain is required, the Rail Infrastructure Manager (RIM) will normally monitor any flood indicator alarms and/or water levels and to take whatever action is necessary to ensure safe rail traffic operations (e.g. speed restrictions, track closures etc.). RTC operating rail traffic on the affected line(s) are to adhere to any instructions received and take whatever other action is necessary to ensure their own safety and the safety of the rail traffic they are operating.
Occasionally, RTC will encounter storms, flash flooding or similar events where advice is not received from the RIM. In these situations, RTC are to observe any water adjacent to the rail infrastructure. Where the water level is such that the sleepers and the supporting ballast is not visible, or there is signs of washouts or scouring on the side of the ballast and/or in the formation (Refer Figure 1, 2 & 3)[72] the RTC is required to stop the rail traffic and advise the NCO and LRC.
Some of the information and procedures from QR and Aurizon have evolved following incidents or in response to previous safety issues identified through ATSB investigations.
Internationally, the Rail Safety and Standards Board (RSSB) provides network rules and standards for the United Kingdom (UK). The rules for managing and operating in floodwaters were detailed in GERT8000-M3 Rule Book, Managing incidents, floods and snow.[73] This rule provided clear details for what drivers needed to report in relation to flooding. Train drivers were also required to stop their train if necessary, to provide that information. Drivers were required to report if they believed floodwater:
is up to the bottom of the rail head
is up to the top of the rail head
is above the top of the rail head
is moving and likely to dislodge the ballast
has dislodged the ballast.
To assist with the driver’s assessment, a diagram was provided detailing the location of floodwaters in reference to the rail and corresponding response (Figure 22). Trains were permitted to operate under normal working if the water was below the bottom of the rail head provided the water was not moving or had not dislodged or was unlikely to dislodge ballast. If floodwater was up to the top of the rail head, operations were restricted to a maximum speed of 10 km/h. Where water was above the top of the rail or was moving and likely to dislodge ballast or has dislodged ballast trains were to stop.
The driver was also required to ensure that if a train had been stabled or passed through floodwater above the bottom of the axle box that network control was advised. The signaller was provided with similar instructions detailing their response to reports of flooding.
Figure 22: Excerpt from GERT8000-M3 Rule Book, Managing incidents, floods and snow
Source: Rail Safety and Standards Board, United Kingdom
Regulatory oversight
Office of the National Rail Safety Regulator
The Office of the National Rail Safety Regulator (ONRSR) was the regulatory agency for rail in Australia. It was not a government agency, but an independent body corporate established under the Rail Safety National Law Act 2012. Its functions were to regulate the rail transport industry in Australia through its rail safety accreditation regime and the Rail Safety National Law (RSNL). ONRSR set requirements for rail safety management systems (SMS), conducted compliance activities including audits and inspections, and enforced the RSNL.
ONRSR advised that they utilised a risk-based approach to regulation as detailed in The ONRSR Way.[74] The regulatory information they collected for the industry and specific operators was utilised to determine their audit and inspection schedule. This was also utilised to set their national priorities. ONRSR advised that some risks associated with extreme weather were considered in their Track Conditions national priority for 2016 and 2017.
ONRSR had undertaken numerous audits and inspections of ARTC to assess the compliance of their safety management system with the RSNL. Between 2016 and the derailment, ONRSR had undertaken nine audits and 64 inspections across ARTC operations. In that period, they issued three improvement notices and 87 non-conformances to ARTC. One of the non‑conformances related to maintenance and recording of defects for drainage systems. That non‑conformance was issued in 2018 and closed in 2019. None of the other notices related to risk management of infrastructure risks or design and maintenance of flood mitigation.
Similar occurrences
There have been multiple occurrences with trains derailing during extreme wet weather due to flooding or encountering floodwaters across Australian and overseas. These occurrences provide learning opportunities for organisations to reduce the likelihood and/or consequences of similar occurrences.
ARTC occurrences
Between 2009 and 2014 the ATSB investigated three derailments due to flooding along the ARTC managed east-west corridor. These were:
Derailment of train 5PS6 near Golden Ridge, Western Australia (RO-2009-003)
Derailment of train 7SP3, Roto, New South Wales (RO-2012-002)
Derailment of freight train 3MP9, East of Malbooma, South Australia (RO-2014-006).
In each of these investigations it was found that the heavy rainfall likely exceeded the design of the drainage culvert leading to overtopping of the track and the ballast washing away. The trains then derailed when they passed over the section of track. Each of these trains was a freight train and only the crew of 5PS6 suffered minor injuries.
There were several safety issues and recommendations associated with these investigations that broadly related to the management of weather monitoring, track drainage and flooding, and lack of a flooding special locations register. To address these issues ARTC engaged the services of the EWN for weather monitoring and introduced the extreme weather monitoring procedure (OPP‑01‑05) initially along the east-west corridor. They also undertook flooding studies along the east-west corridor to assess the risk of flooding and installed culvert flow monitoring equipment at high-risk locations.
In relation to not having a register to record flooding special locations (RO-2014-006), ARTC advised that they were upgrading their electronic asset management system to optimise inspection and maintenance activities including recording of special locations.
On 27 December 2011, freight train 7AD1 derailed at the Edith River bridge near Katherine in the Northern Territory. A section of the embankment had been washed away by flooding that exceeded the 100 ARI flooding that the bridge had been designed for. It was found that the rail infrastructure manager did not have a system in place to monitor the river height at the bridge although information was readily available. It was also found that there were deficiencies in the procedures and training for the responses to severe weather events and the warning system in place was ineffective.
On 27 December 2015, a severe thunderstorm led to heavy rainfall near Julia Creek on the Mount Isa rail line in Queensland. The network control officer (NCO) was aware of the storms and had received reports from train crew and arranged a track patrol. The crew of freight train 9T92 were travelling towards Julia Creek when they observed a section of track that had been previously flooded but the water had receded. They then encountered another section that had been flooded, however, the flooding had scoured the ballast and compromised the integrity of the track. It was too late for the driver to stop once they sighted the washout and the train derailed. The lead locomotive rolled as it derailed and all 26 wagons containing acid also derailed.
It was found that reporting procedures implemented by Queensland Rail and Aurizon provided insufficient guidance to the NCO or rail traffic crew to identify and respond to potential hazards from a wet weather event.
Both Queensland Rail and Aurizon issued safety alerts to improve the effectiveness of their existing network rules and procedures.
On 7 March 2018, freight train 6792 encountered floodwaters at the Little Banyan Creek rail bridge in Queensland. A condition affecting the network (CAN) had been declared due to a wet weather event. The crew of freight train 6792 were required to operate at a controlled speed[75] due to the CAN for a significant part of their journey. While travelling at 50 km/h the train rounded a curve and encountered floodwaters at Little Banyan Creek that was under 0.6 m of flowing floodwater.
It was found that while there was weather monitoring equipment at the creek it had been out of service. Additionally, while there was a closed-circuit television camera (CCTV) to monitor the water levels, the illuminator to enable effective operations at night was also out of service. The network personnel were not aware that the weather monitoring equipment and illuminator were out of service and were expecting an alert and did not actively search for information.
It was also found Queensland Rail had no restrictions on the distance or time that controlled speed could be used as a risk control during CANs. The effectiveness of the control had the significant potential to deteriorate over extended periods due to workload, vigilance, fatigue and risk perception. Additionally, Aurizon’s procedures and guidance for two-driver operations during CANs did not facilitate effective sharing of duties.
Following the occurrence, Queensland Rail improved the processes and procedures for ensuring the reliability of weather monitoring systems and awareness of network control personnel of faults. Aurizon also undertook a review of its procedure for the management of workload for two-driver operations during CANs.
On 12 August 2020, a high-speed passenger train[76] derailed near Carmont, United Kingdom. Prior to the derailment, there had been significant storms causing extensive flooding and landslips. There were four landslips within close proximity to the derailment site that were known to network control prior to the derailment. While known, there was no clear requirement to operate at a reduced speed. The passenger train was authorised to operate at normal speed and derailed at 117 km/h after passing over a section of track that was covered by gravel.
The gravel had been washed onto the track from a drain near the rail line. The lead power car derailed and then stuck a bridge parapet a short distance ahead of the washout. This caused the power car to veer off the bridge, and down an embankment. All passenger carriages derailed and jack-knifed with some coming to rest on the side or roof. The fourth carriage remained upright but came to rest on top of the first carriage.
There were two train crew (train driver and conductor) and seven passengers on board at the time of the derailment. Both train crew and one passenger were fatally injured in the derailment. All other passengers were injured. Due to Covid-19 restrictions there were less passengers on-board and it was estimated that there would normally have been between 25-50 passengers.
The immediate cause was that the drain had not been installed in accordance with the design leading to the gravel surrounding the drain washing out and onto the rail line, the train then passed over the gravel and derailed.
There were several findings relating to the way that the rail infrastructure manager responded to and managed the risk of extreme rainfall, some of these were:
They have not addressed weaknesses in the way that it mitigated the consequences of extreme rainfall events. The underlying reasons for this were:
They had not recognised that their existing measures did not fully address the risk of extreme rainfall events.
Their assurance processes did not identify the areas of weakness in the implementation of their extreme weather processes or that the controllers lacked the resources and skills necessary to manage complex weather events.
They had not clearly identified weaknesses in their operational mitigation measures to manage the risk of earthworks and drainage failures.
While they were aware of the risk, they had not completed the implementation of additional control measures following previous extreme weather events.
There were 20 recommendations associated with the investigation for the improvement of rail safety. The recommendations were aimed at managing extreme weather events, civil engineering construction, assurances for railway control, train design, and applying learnings from previous events.
Safety analysis
Overtopping and washaway
The embankment at the derailment site had been identified as at risk of overtopping during rainfall events of 10-20 Annual Recurrence Interval (ARI) due to the capacity of the culvert at 643.849 km as part of the 1995 culvert assessment study.[77] The 24-hour rainfall recorded by the BoM of 310 mm on 25 February 2021 at Nana Glen, corresponded with an overall rainfall event between 20‑50 ARI (5% and 2% AEP) for that location (Table 11). The actual rainfall was over a shorter duration with varying intensity across the broader area.
The simulation of the rainfall accumulations from the Grafton radar suggested that in 6-hours leading up to the derailment, rainfall of between 200‑300 mm may have fallen near the derailment site (Figure 13). The 6-hour rainfall event may have been between 100‑200 ARI (1% and 0.5% AEP) and possibly exceeded a 500 ARI (0.2% AEP) for that location (Table 11). The actual duration and intensity of the rainfall could not be determined, although, exceeded ARTC’s threshold for black alerts and their infrastructure standards.
The location of the culvert at 643.849 km nearest to the derailment site would likely have been affected by rises in the Orara River with water flowing up Cowans Creek and into the field on the southern side of the embankment. During periods of no or light rainfall in the Cowans Creek catchment, the effect of the Orara River would have been minimal, however, if heavy rain occurred the effect could have been significant as outlined below.
The culvert outlet invert was at an elevation of 63.45 m while the banks of the Orara River were at approximately 60‑61 m. Rises in the river level above 5 m would likely have filled the entirety of the culvert as the inlet obvert was at an elevation of about 65.66 m.
Culverts can accommodate increases in headwater; [78] however, the headwater cannot be increased indefinitely without overtopping occurring. The level of rail infrastructure damage depends on the height of the headwater and velocity of water flowing across the track structure.[79] The height of the tailwater[80] also influences the damage on the downstream side of the embankment. Where there is a large difference in height, the velocity of the water flowing down the structure can be high and erosive.[81] Scouring of the embankment as well as the culvert outlet can occur under these conditions.
On the night of the occurrence, the culvert at 643.849 km did not have sufficient capacity to discharge the runoff water from Cowans Creek to the Orara River. Between the time of NT31 passing around 0110 and train 4BM4 arriving at Nana Glen at 0137, floodwater began to overtop the embankment (Figure 23).
Once the water began to overtop the embankment, its velocity increased and began to scour the ballast around 643.800 km on the downstream side. The scouring continued progressively getting wider with the ballast, as well as some of the subgrade material washing away (Figure 24). The scouring of the ballast and embankment continued for some time after the derailment until the headwater level receded below the top of the embankment.
Figure 23: Overtopping and washaway
The diagram (not to scale) depicts the overtopping of the embankment and process of ballast scouring. Initially the ballast on the downstream side would have washed away before all ballast was displaced. The headwater from Cowans Creek is depicted as a blue line while the possible tailwater and floodwater level from the Orara River is shown as solid blue.
Source: OTSI
Figure 24: Ballast washed away
The image shows an area of the embankment where the ballast had washed away with the sleepers resting on the subgrade material. The vegetation can be seen to be lying flat due to the flow of water over the embankment.
Source: ARTC, annotated by OTSI
The rainfall recorded for Nana Glen by the BoM was on the opposite side of the Orara River, approximately 1.5 km from the derailment. Based on the Grafton weather radar, it was probable that similar rainfall fell within the Cowans Creek catchment on the night of the derailment. The Orara River height at Glenreagh was recorded as rising rapidly from 2.75 m at 2000 on 24 February and reached 6.98 m by midnight. By 0100 on 25 February the height was recorded as 8.15 m, this rose to 8.59 m by 0130 (Table 4). The rainfall alone, would almost certainly have resulted in the overtopping of the embankment. However, the severity was probably increased due to the combination of both the rainfall and rises in the Orara River.
Derailment
At interview driver A reported observing water in and around the rail corridor after passing through Glenreagh. The track speed in the Up direction for freight services was 70 km/h in this section. The train speed was maintained between 65-68 km/h until around 646.010 km. The speed decreased to 63 km/h and then down to 56 km/h at 644.110 km. The train was powering through the section and throttle was maintained between notch 1 and 5. On approach to the derailment site, the speed was increasing and was in throttle notch 5. The conditions at the time were dark, it was raining and the headlights on 4BM4 were on. The track curvature would have provided limited sighting distance for the section of track ahead. The driver reported that there was no indication of a track issue and on exiting a right-hand bend the locomotive suddenly dipped as they passed over the washaway.
The front of train (FOT) footage showed two areas that were washed away as 4BM4 was approaching (Figure 5). As the train passed the washaway, the lead locomotive dipped around 300 mm as there was no ballast to support the weight of the loaded train. The locomotive continued and bounced out of the washaway before coming to a stop. With the continued scouring of the ballast the two areas washed away and joined to become one after the derailment.
The third locomotive and first 10 wagons derailed at the washaway with some wagons and containers entering the floodwater. The trailing portion of the train came to a stop due to the loss of the brake pipe air.
Driver A reported thinking at the time that it was safe to proceed given they had just passed two other trains that had been through the area and not been advised of any issues. Driver D recalled contacting 4BM4 as part of the roll-by inspection on passing at Kungala. Driver A believed they would have spoken to them but could not remember. There had been no communication with the passing trains in relation to the weather or track condition, and they had not received or reported a CAN. At the time Driver A felt the conditions they had observed prior to the derailment did not warrant a CAN.
Driver B recalled that they did not see any floodwater but on approach to Nana Glen were looking out for the distant signal. The water that was observed by driver A was primarily on the left‑hand side and would probably have been harder to see from a seated position for the second driver.
It is probable that if actions were taken to slow the train when it first encountered the water building up near the rail head, the train could have either stopped or at least slowed prior to encountering the washaway. If the train had not been able to stop, the train may still have derailed but the severity would have been significantly reduced.
Guidance for extreme weather and flooding
Under ARTC network rule ANGE 206, network users were required to report conditions affecting the network (CAN). Train crew were required to report ‘Conditions that can or do affect the safety of rail operation’ to network control. On the night, the network users and train crews had not received advice about the extent of the weather event or the amber alert.
The drivers of 3MB4, NT31 and 4BM4 were found to all have different interpretations of what ‘conditions can or do affect the safety of rail operations’ meant, especially when operating in extreme wet weather and flooding. While only driver A observed floodwater on approach to Nana Glen, each of the drivers had a different understanding of when trains were required to either stop or report floodwater in the rail corridor (Table 12).
Table 12: Drivers’ observations and understanding wet weather and flooding
Driver
Observation
Understanding
4BM4 - A
Visibility affected by extremely heavy rain. Water building up in the rail corridor and began to build up near the rail head about 1-1.5 km before the derailment.
Trains could continue providing water was not over the top of the rail.
4BM4 - B
Visibility affected extremely heavy rain and condensation on the window. Did not see floodwater.
Trains could continue providing water was no more than 100 mm above the rail head or they had not been advised by network control to stop. Reported concern if water was more than 100 mm above rail was due to the traction motors.
NT31 - C
Visibility affected extremely heavy rain. Did not see floodwater.
Would report floodwater if seen in the corridor and would be concerned if water was seen near the rail.
3MB4 - D
Visibility affected extremely heavy rain. Did not see floodwater.
Trains could continue providing the water was below the rail head as once the water was above this level it could get thrown up into the traction motors. Would report to network control if water was running over the track or if seen on the ballast approaching the rail.
The drivers were unable to detail how they had formed their understanding of the rule or indicate where it was documented. The CAN network rule was broad and open to interpretation by rail traffic crews as to what was to be reported to network control. None of the drivers considered the conditions on the night warranted a CAN and they did not report a CAN. Given the drivers’ of NT31 and 3MB4 understanding of what and when to report to network control, if they had sighted floodwater on passing through Nana Glen, they may not have reported the conditions to the NCO prior to 4BM4 arriving.
The absence of guidance to train crew on how to respond to extreme wet weather and flooding increased the risk of adverse events. Had the drivers of 3MB4, NT31, 4BM4 (or any other train) reported the extreme rain prior to the occurrence, it would have provided an opportunity for the NCO to become aware of the increased risk of flooding and to have implemented possible actions. In addition, clear guidance for when trains must stop or slow if floodwaters are encountered in the corridor would likely reduce the severity of the derailment. Without clear guidance, what conditions were to be reported was open to the interpretation of each driver and rail operator.
ARTC did have some details within their original weather monitoring procedure (OPP-01-05) relating to high water. The TTM was to advise train crew of the following for amber alerts:
High rainfall is expected in the ‘XXX to YYY’ region. Network users are reminded to drive to the conditions and report unusually high water levels adjacent to the track.
If a red alert was issued, the TTM was required to advise train crew of the following:
Very high rainfall and rapid stream rises is forecasted in the ‘XXX to YYY’ region. Network users are required to drive at speed that will enable to stop within ½ the distance that can be seen and report unusually high water levels adjacent to the track.
Train crew were also required to report unusually high water adjacent to the track, bridges and culverts. When the procedure (OPE‑PR‑014) was expanded in 2017, the requirements to warn rail traffic for amber alerts were removed. The details for what was reportable by train crews, as well as requirements for a reduction in speed were removed altogether.
As the rail infrastructure manager (RIM), ARTC had not defined the requirements or communicated what was reportable on their network for flooding events. ARTC had not provided any information or guidance to rail traffic crews operating in extreme wet weather or how to respond to flooding.
A review of some other rail operators and RIMs indicated that they have issued guidance material and safety alerts for operating in extreme weather and for reporting floodwater in the corridor. This material contained clear criteria to assist train crew operating in extreme wet weather and for reporting floodwater in the corridor, on the formation or covering the ballast, sleepers or rail.
Rail traffic crews were responsible for the safe operation of trains through ARTC’s network in accordance ANGE 232. This rule did not require rail traffic crew to reduce their speed if visibility was affected unlike RISSB ANRP 2027 or NSW Trains NTTWP 100. It was a requirement of these rules (ANRP 2027 and NTTWP 100) that if visibility was affected, trains were to slow to maintain safety, reflecting industry best practice. ANRP 2027 also contained specific requirements for rail traffic crew to pay particular attention when approaching a level crossing.
Trains NT31 and 3MB4 were the last two services that travelled through Nana Glen prior to train 4BM4 derailing. Both drivers reported that they experienced extremely heavy rain between Coramba and Glenreagh that affected their visibility. With their visibility severely affected by the weather, the drivers would have had a reduced opportunity to sight signals, potential obstructions or safely traverse the level crossings between Coramba and Glenreagh. The drivers relied on their knowledge of the route and location of signals to continue without reducing their speed.
The Pacific National (PN) train drivers were qualified to a Certificate IV in Train Driving and had undergone training in TLIF4410 Respond to abnormal situations and emergencies when operating rail traffic. The training material for this module provided general information but tended to suggest that network control would advise of abnormal situations. Weather was detailed as a potential abnormal situation with no further information for how train crew were to respond. PN had not provided their train crew with guidance for how to respond to extreme wet weather or flooding. There were no explicit requirements to reduce speed if visibility was affected or any details for what constituted a reportable condition in relation to weather or flooding.
Extreme weather monitoring procedure and response
Detection and communication of alerts
Weather forecasts and alerts issued by the EWN were communicated to ARTC personnel through several different methods. The daily forecast was typically sent between 0800 and 0900 by email. Receiving the forecast would be predictable and easily adapted to daily routines. The daily TAR corridor forecast issued by the EWN on the morning of 24 February was distributed to the network users and operators (internal and external stakeholders) by the dayshift Train Transit Manager (TTM) at 0922. The email from the TTM contained the note to ‘please pay extra attention to the area Northern NSW’. At 1114 the same TTM resent the forecast to network users and operators with the same note.
The mechanism (email) for advising those who were required to take action in response to an amber alert, would not have ensured that such personnel would have always been made aware in a timely manner. Weather alerts could be sent at any time and amber alerts were only required to be sent via email. These alerts required action but could be missed, in particular by network control personnel after hours.
While not a requirement of ARTC’s weather monitoring procedure, some personnel were configured to receive text messages to their phone for amber alerts from the EWN. On the night, the amber alert issued at 2159 was communicated by both email and text message. The text message went to numerous infrastructure maintenance personnel including the Corridor Manager (CM) and Area Manager (AM). The Service Delivery Manager (SDM) also received the message, however the CM, AM and SDM were not working at the time but on-call personnel were available. The TTM and Network Control Officer (NCO) were not configured to receive text messages and did not receive the alert to their phone.
Network controllers were not on the email distribution list to receive weather alerts or forecasts from the EWN. The NCOs would only have received weather alerts if they were detected and communicated by the TTM. If the TTM did not detect an alert, or did not detect it in a timely manner, then neither the alert nor potential risk to the network would be known by the NCO.
The TTM could not recall if they had seen the amber alert issued by the EWN at 2159 before or after the derailment but did confirm that the alert was not communicated to operators and network users as required.
Both Pacific National (PN) and NSW Trains confirmed they had not received any severe weather alerts from ARTC in the days prior to the occurrence. Reviewing the alerts issued by the EWN in the 72 hours prior to the derailment, there should have been at least three occasions where PN and NSW Trains were advised.
If the weather alerts had been communicated to the network users by the TTM, this would not necessarily have ensured that the train crew operating in the area would have received the alert. Neither PN nor NSW Trains had a process to actively communicate weather alerts to their crew once they were in-service. Both relied on ARTC to advise when it was unsafe to operate trains, their train crew to report conditions affecting the network (CAN), or to be advised by the NCO of a CAN.
The nature of train control is that in most instances, the controller is operating remotely from the trains under their control. Unless the control personnel actively searched for weather information or received alerts, they would have been unaware of the risk to the network.
On the night there were no other alerts communicated to ARTC by EWN for the evolving weather event along the north coast (Table 3).
The crews of trains 4BM4, NT31 and 3MB4 had not been advised of the weather event or received any information from the NCO prior to the derailment. While these crews experienced extremely heavy rain this was not reported to the NCO, reducing the controller’s awareness of the local conditions.
Red and black alerts issued by the EWN were more likely than amber alerts to be detected in a timely manner by ARTC personnel. Some personnel would receive text messages to their phone and the network control centre would receive an automated voice message to communicate the red and black alerts.
Response to rainfall and flooding - amber and red alerts
The responses to rainfall and flooding (amber and red) alerts were divided between the Defined Interstate Rail Network (DIRN) and Hunter Valley (HV) network, with the DIRN then divided into two corridors, east-west and north-south. The full details for each network are in Appendix A – OPE-PR-014 response tables. The design of ARTC’s colour coding in the tables was to classify the perceived risk to the network. Colour coded alerts could be for forecast weather, BoM weather warnings or if rainfall exceeded an ARI threshold.
Weather forecasts were based on the best judgement and assessment of the EWN meteorologist using the information available to them. These may or may not have been accurate when compared to actual weather conditions which could be vastly different to forecasts. The forecast on the morning for the TAR corridor was coded as green with two sections north of Grafton coded amber (Figure 10). The actual weather event on 24‑25 February far exceeded the forecast conditions from the BoM and EWN.
Under procedure (OPE-PR-014), the ARTC’s Extreme Weather Group (EWG) was only required to meet and determine the response to red or black forecasts. Any standalone weather alerts were the responsibility of individuals to respond to without the requirement of the EWG. There was no EWG on 24 February nor was it required based on the forecast.
ARTC’s procedure did not distinguish between the responses to forecast and actual extreme weather events. The procedural response to a weather alert for a forecast event (amber, red or black) was the same as to an alert generated by actual rainfall exceeding the ARI threshold. So, for decisions based on a forecast, there was time to review and consider other factors as the threat was not imminent. In contrast, if the red or black alert was triggered for actual rainfall exceeding the ARI threshold, the threat to the network would likely be more immediate and require a more rapid response.
The EWN would generate a red or black alert if rainfall exceeded an ARI threshold, however detection of this also relied on sufficient weather monitoring equipment in the area. While an alert would be generated, the location of the weather station, proximity to the rail line, topography of the area, track drainage features, as well as ground saturation, would all have influenced the level of potential risk to the network. These risks were not addressed as part of the procedure or responses for amber and red alerts. If a black alert was issued all operations were to cease in the area, once stopped, the immediate risk to people and trains in the area would likely be mitigated.
Without sufficient weather monitoring equipment to monitor the actual conditions, the process relied on reports from train crew, maintenance personnel or the results of track inspections to identify and mitigate any operating risks related to localised weather conditions.
In response to an amber alert the only action required by the TTM was to communicate the alerts to network users. There was no requirement for ARTC to advise train crew operating through an affected area of amber alerts for rainfall and flooding. For this occurrence, the TTM should have advised the network users by email, but there was no direct notification to the train crew by ARTC.
If a red alert was issued by the EWN, the TTM was required to ‘Ensure communication to trains and network users through the affected area’. In practice, the NCO for the affected area was required to communicate this to train crew. However, before the NCO could advise train crew, the alert would first have needed to be detected and communicated to them by the TTM. The subsequent communication to train crew may or may not be in the form of a condition affecting the network (CAN). There was no further information detailing how this information was to be communicated to train crew or what level of information was required. And, in any event the TTM did not advise the NCO of the alert in this incident.
ARTC advised they also utilised information from train crew reporting a CAN or reports of flooding to inform their response. However, what was reportable as a CAN was open to interpretation by train crew. On the night, there were no reports in relation to the extremely heavy rain in the area from the train crew. (See Guidance for extreme weather and flooding for further analysis relating to train crew reporting weather and flooding).
For red alerts, the TTM was also required to consider trains that should be held or moved to ‘safe’ locations. The procedure did not detail how a location would be assessed as ‘safe’ or require the considerations and assessment to be documented.
The responses for both the DIRN and HV network as defined in procedure OPE-PR-014 were similar, with some differences based on the different role descriptions or network control organisational structure. One difference of note between the DIRN and HV, was that in response to an amber alert, the HV TTM was required to actively search for weather information from the BoM and State Emergency Service (SES). This was not a requirement for the DIRN and the TTM advised at interview that they solely relied on alerts from the EWN. ARTC were unable to explain why there were differences in the procedure between the two networks.
For amber and red alerts, the Corridor Managers (CM) were required to consider several actions including higher frequency inspection and inspection of culverts. While they were to be considered, there was no requirement to act or to document what had been considered. Track patrols were to be considered for both amber and red alerts but were not mandatory. The CM advised that they would not have commenced track patrols for an initial amber alert but would have waited for other alerts or reports of rainfall. If a red alert was triggered by rainfall exceeding a threshold then they would have considered track patrols. The time to initiate a track patrol would have varied depending on the location of the alert and availability of on‑call personnel. There were no procedures to assist the CM to determine whether trains were required to slow or stop until the track was inspected.
At interview the CM detailed how they would position personnel across their network in preparation for larger events. These would typically be for red or black events that had been forecast. The purpose of this was to undertake inspections or monitor the performance of areas of known weather related risk. This relied on ARTC having already identified areas that were susceptible to flooding and on the local knowledge of maintenance personnel as there was no documented flooding special locations register. Such reliance would not have been a reliable process to manage the risk or ensure areas at increased risk of flooding were monitored.
For amber alerts, the Area Manager was required to collect information from maintenance crews and develop a local response plan. If a red alert was issued, they were required to implement that plan. On the night there were no inspections of the TAR corridor by infrastructure personnel in response to the amber alert.
ARTC’s procedure made specific reference to consider ‘more frequent and/or targeted track inspections with focus on known ‘high risk’ areas’. It was not clear how these known ‘high risk’ areas were determined or assessed as ARTC did not have a flooding special locations register for the TAR corridor or NSW rail network as required by its safety management system (SMS). See Flooding special locations on page 66 for further analysis on flood risk.
Both ARTC and the CM advised that some of their personnel used weather information from sources other than the EWN. These included the BoM, ARTC weather stations and social media groups. While these proactive steps could assist with developing a broader understanding for some, they were not part of a documented process or ARTC’s SMS, and as such were inconsistent in application and response. There were several alerts issued and publicly available from the BoM and SES prior to the derailment. If ARTC personnel were monitoring those, they were either not detected or not actioned. At interview the TTM advised that they solely relied on the alerts from the EWN and they were not required to actively search for information.
The evidence supports that the response to amber alerts in practice was to wait for additional alerts or information before acting. In locations where there was sufficient weather monitoring equipment (weather stations/stream flow detected) to report on actual conditions, this may have appropriately managed the medium risk of an amber alert. However, without this equipment or active monitoring of the actual conditions, weather events that exceeded the medium risk of amber could have gone undetected. While responses to red alerts were intended to be more proactive, they did not require specific action to manage the higher risk to the network.
Response to wind alerts
The risk posed by wind was different to the risk of rainfall / flooding. The risk to rolling stock from these risks is largely dependent on the train type (passenger, freight – single or double stacked, road-rail vehicles and track machines). Where there was an active wind alert (amber, red or black) ARTC’s procedures required train crew operating through the area to be advised of the alert. This requirement differed from amber rainfall events which did not need to be reported to the crew.
EWG meetings were only required for black wind alerts. The response for the Hunter Valley (HV) (Table 17 - Appendix A – OPE-PR-014 response tables) noted EWG meetings as a requirement for both red and black alerts which was incorrect. When the procedure was revised, the removal of EWG meetings for red alerts was not updated in the procedure.
ARTC and EWN weather monitoring service
Weather alerts prior to derailment
The EWN issued the daily forecast for the TAR corridor on the morning of 24 February, this detailed a low chance of severe thunderstorms (10-30 per cent) for the area between Coffs Harbour and Grafton. The actual event far exceeded the forecast for this area.
The weather alerts were issued to ARTC personnel based on the BoM forecasting districts applicable to the corridor section. Alerts for the TAR corridor consisted of:
The alert issued by the BoM at 2152 was applicable to NSW districts 1 and 2. The threat map showed the warning area away from the rail corridor (Figure 11). The second alert issued by the BoM at 2208 was also applicable to those two districts. The second threat map showed a large section of the corridor could be impacted. The EWN advised that they issued the alerts based on the districts affected rather than on the threat map area. If subsequent alerts were issued by the BoM but with the same description then it would not have been communicated to ARTC. The intent of this was to reduce unnecessary alerts being communicated which could potentially de‑sensitise the receivers.
The EWN utilised an alert generator (software program) to assist with generating and distributing weather alerts to their clients. Most severe thunderstorm warnings issued by the BoM were set to a threat level of amber by the EWN. The EWN advised this was based on the title description and some key terms or phrases used within the BoM alert. If the subject of the alert referenced giant hail, destructive winds or tornado, the alert would automatically have been set to a threat level of red.
The title of both alerts issued by the BoM at 2152 and 2208 referred to heavy rainfall, damaging winds and large hailstones. While the key words did not change, the phrasing of the rainfall intensity within the body of the alert did. The first alert referred to ‘heavy rainfall that may lead to flash flooding’ while the second alert referred to ‘intense rainfall that may lead to dangerous and life-threatening flash flooding’. The BoM advised that the change in phrasing was based on their definitions for rainfall:
Heavy Rainfall - Rainfall over a period between 30 minutes and 6 hours which exceeds the 10% AEP [Annual Exceedance Probability] depth.
Intense Rainfall - Rainfall over a period between 30 minutes and 6 hours which exceeds the 2% AEP depth.
At the time of the derailment, the EWN’s alert generator was not configured to detect the changes in rainfall intensity or references to life-threatening flash flooding used by the BoM. The escalation was not detected at the time and there were no further alerts sent to ARTC on the night. The EWN advised that the BoM had not communicated the change in wording of their alerts or their use of the term life-threatening flash flooding. The EWN reported they were aware of the change which occurred about 18 months before the derailment. The EWN advised they had not seen many examples of where the terms had been used prior to the derailment, so had not changed their program.
The second alert from the BoM referred to rainfall that exceeds the 2% AEP over a duration of 30 minutes to 6 hours. When compared to ARTC’s risk matrix this corresponded to rainfall that may have exceeded the minimum threshold for black alerts 50 ARI (2% AEP).
Once alerts were communicated by the EWN, it was up to ARTC personnel to assess if areas of the rail corridor could be affected and what actions were required. The alert issued at 2152 by the BoM stated flash flooding may occur at Glenreagh. The Orara River ran in close proximity to the rail line at both Glenreagh and Nana Glen. The BoM subsequently issued flood warnings for the Orara River but ARTC was not aware of them.
The BoM weather station at Nana Glen that recorded the 310 mm of rain was not being monitored by the EWN. This station reported on a 24-hourly basis, and the 310 mm of rain was reported about 7.5 hours after the derailment. The EWN advised that on the night of the derailment the rainfall gauge at Boyles Bridge[82] that they monitored was offline between approximately 2100 until 0600. If the gauge had been working, it may have triggered a rainfall threshold based on the weather radar.
Service agreement
ARTC had engaged the services of the EWN for weather monitoring of the east-west corridor of the DIRN around 2013. Weather monitoring criteria used by EWN was defined in ARTC’s original extreme weather monitoring procedure (OPP-01-05).
In 2017, ARTC introduced an expanded procedure (OPE-PR-014) to include the DIRN north‑south and HV corridors. Prior to finalisation of that procedure, ARTC requested a proposal from the EWN to extend the weather monitoring services they were already providing for the east‑west corridor to the north-south and HV corridors. The requested EWN proposal was accepted by ARTC. The ARTC understood the requirements of its expanded procedure (OPE‑PR‑014) would be applied to the east-west, north-south and HV corridors under the new service agreement. At the commencement of the new service agreement, ARTC provided information to the EWN that was needed to configure the additional network areas (north-south and HV) to meet ARTC’s specifications for weather monitoring under OPE‑PR‑014.
In 2018, ARTC identified that weather monitoring for the HV corridor was not being performed for the entirety of the corridor as expected under the contract with EWN. To address this, EWN provided a new proposal which was accepted by ARTC and the service agreement (CA‑SA‑05445‑00) was amended to include the missing areas. During the process of resolving the issue, ARTC again provided the information requested by the EWN to configure the additional network areas. On 20 December 2018, the EWN advised that weather forecasting for the HV corridor was scheduled to commence on 2 January 2019. In this same correspondence they advised that the alerts were operational.
Contract CA-SA-05445-00 expired in March 2020. In July 2020, ARTC requested a further proposal from the EWN based on delivery of their existing service. That proposal formed the basis of a new contract (CA‑SA‑06312-00) and was awarded in August 2020, 6 months prior to the derailment at Nana Glen. This contract included provision of forecasting and rainfall monitoring, as well as culvert flow and weather alerts for the entire ARTC network.
It was found that while forecasting commenced in 2019 for the HV corridor, alerts for rainfall exceeding the ARI thresholds had not been set up by the EWN at that time. The alerts referred to by the EWN as being operational (at commencement on 2 January 2019) were weather alerts based on the BoM districts rather than the rainfall monitoring that was defined in the new contract and expected by ARTC.
While ARTC had provided the information required by the EWN including the ARI thresholds, rail corridor boundary and distribution list needed to set up for these types of alerts. It was not clear why the set up for monitoring of rainfall depths for the HV corridor had not been completed by the EWN in January 2019. This issue had not been identified by ARTC at the time or during the subsequent contract replacement in July 2020.
ARTC’s extreme weather monitoring procedure (OPE-PR-014) required rainfall durations of 1 hour, 6 hours, 24 hours, and 72 hours to be monitored. These values were reflected in the 2017 contract (CASA-05445-00) between ARTC and the EWN. The duration of 30 minutes was also included although no values were noted within ARTC’s procedure. When that contract was replaced in 2020, the duration of 72 hours was not included in the contract by EWN and this was not detected by ARTC.
At the time of the derailment, the EWN were monitoring rainfall durations of 1 hour and 6 hours but not 24 hours as required by the procedure and contract. The EWN advised that when they initially commenced monitoring for ARTC the longer durations were being monitored but that it stopped after verbal feedback from ARTC that it may not have been useful, although they could not confirm when. EWN reported that they found the longer durations would generally trigger the ARI threshold after a rainfall event when the immediate risk of flooding was perceived to have passed. Post incident, ARTC confirmed that they expected the rainfall durations to be monitored in accordance with their procedure.
From 2017 to 2020, the EWN provided several proposals (quotes) in response to requests or changes of requirements from ARTC. Each of these proposals contained similar references to the EWN providing a ‘tailored solution’ to meet ARTC’s requirements, without further detailing how that was delivered. On each occasion that ARTC asked for a proposal, it was provided with the same service details becoming the service contracts (CA-SA-05445-00 or CA‑SA‑06312‑00). There may have been further discussions and reviews as to what the ‘tailored solution’ consisted of when the EWN were initially engaged for the east-west corridor. However, it was not done in sufficient detail for the expanded service for ARTC to understand if the ‘tailored solution’ met its new procedure requirements.
There were several differences between the services the EWN were providing, what was in the service agreement and in the ARTC’s extreme weather monitoring procedure (OPE-PR-014). ARTC had not undertaken any audits or inspections of EWN and these differences were not known to ARTC.
Risk matrix and rainfall thresholds
ARTC advised that the risk matrix (Table 9) from their weather monitoring procedure was the basis of EWN’s colour coding of rain / flooding and wind alerts. This risk matrix detailed the criteria for the alerts with a corresponding colour code for the perceived level of risk.
Records of the risk matrices used by the EWN were requested. Two different versions of the risk matrices were used internally at EWN and by different people. While both documents broadly aligned, there were some minor differences relating to the probability of severe thunderstorms used for the purpose of forecasting. When the two versions were compared against ARTC’s risk matrix (Table 9), they did not directly align to ARTC procedure (OPE-PR-014, version 3.4) or the original procedure (OPP-01-05) for the east-west corridor.
ARTC’s procedures had divided the network into 50 different geographic areas with corresponding rainfall depth thresholds assigned to each area. The DIRN consisted of 35 geographic areas and the HV corridor consisted of 15. The information for the rainfall depths for each area on the ARTC’s network had been provided to the EWN by ARTC. The EWN had configured the east‑west corridor areas within their weather monitoring software however the new corridor sections (north-south and HV geographical areas) had not been added when ARTC expanded their procedure (OPE‑PR‑014) in 2017.
The EWN provided to OTSI the thresholds they used for monitoring rainfall depths for ARTC on the east‑west and north-south corridors. Although the EWN were provided with the specifications for the 35 geographic areas for the DIRN, they had combined different areas based on the latitude and longitude and were only monitoring 15 areas for rainfall depth (see Appendix B – ARTC and EWN rainfall monitoring areas). The rainfall thresholds used by the EWN for the DIRN did not directly align to the thresholds specified by ARTC. In some areas the EWN thresholds were the same or lower than what ARTC had identified, while higher in other areas. Specifically, along the TAR corridor between Port Macquarie and Coffs Harbour, the EWN thresholds were higher when compared with ARTC’s procedures for red and black alerts:
Red alert
1 hour – 5-10 mm higher
6 hour – 18-27 mm higher
Black alert
1 hour – 7‑10 mm higher
6 hour – 18-35 mm higher.
Alerts in these areas would not have been triggered until rainfall had exceeded the higher EWN threshold. The differences were more significant for the 6-hour durations for red and black alerts. This increased the amount of flooding that could go undetected and so increased the likelihood that the integrity of the network would have been affected.
Although rainfall depth monitoring was detailed in the service agreement for both the north-south and HV corridors, it was found that rainfall depth monitoring for the HV corridor had not been configured within the EWN’s monitoring software. The 15 geographic areas for the HV corridor would not receive red or black alerts when rainfall exceeded the ARI threshold specified within ARTC’s procedure. These 15 areas would still have received weather alerts if issued by the BoM but not when rainfall exceeded design thresholds specified by ARTC.
It was also found that the EWN were only monitoring the durations of 1 and 6 hours for the DIRN. The longer durations of 24 hours and 72 hours were not being monitored as per ARTC’s procedure (OPE-PR-014) or as expected by ARTC.
The EWN also had two different versions of the ARI rainfall depths for the ARTC network. The second version included the durations of 24 hours and 72 hours, but this was not in use. There were no document control details for either version of the risk matrices or the ARI rainfall depths. It was not clear how changes were managed by the EWN.
Flood warnings
The ARTC risk matrix (Table 9) detailed flood warnings issued by the BoM:
Amber - BoM Flood Alert, Watch or Advice issued
Red - Flash flood or generalised flood warning by BoM
Black - BoM warning of Moderate or Major flooding in the region.
While detailed in the risk matrix, the EWN did not issue flood warnings to ARTC as standalone alerts as this was not in the service agreement. The EWN advised that flood watches and specific flood warnings were communicated to ARTC as part of the daily forecast.
ARTC advised that they thought, given BoM flood warnings were included in the risk matrix, that they would have received flood warnings from the EWN as they were occurring. The two flood warnings issued by the BoM at 0003 and 0034 on 25 February for the Orara River, were not communicated to ARTC by the EWN, nor were they required to be under the service agreement.
Remote weather monitoring equipment
At the time of the derailment, ARTC were installing remote weather monitoring stations along the TAR corridor. In total, 14 locations were identified for weather station installation. Two stations had been installed at the time of the derailment, with one at Craven and one at Nana Glen. Neither weather station had been commissioned.
Although ARTC had a standard for determining the need for automatic rainfall monitoring (ARM) it was not used to assess or determine where weather monitoring was required prior to the derailment in 2021. This standard also required ARTC to reassess the need for ARMs as well as the effectiveness of existing stations at least every two years. While the original intent in 2014 was to install weather monitoring equipment along the TAR corridor to monitor temperature, there had been no assessment since that time of the need for rainfall monitoring in accordance with the ARM standard.
ARTC advised that the placement of weather monitoring equipment was intended to provide sufficient coverage of their network. The weather information would then be available to the EWN for monitoring as well as to trigger alerts if rainfall exceeded the ARI threshold for that location. The CM recalled that there had been some discussions and meetings to determine the locations but was unable to provide any documentation. They advised that some consideration was given to monitoring the extremities of their network, and to provide some coverage between the provisioning centres.[83] The final locations for the installation of the 14 weather stations along the TAR corridor were selected using local knowledge and in areas that had access to a power supply.
Although ARTC had installed a weather station at Nana Glen, there was no specific evidence to support why this location had been chosen over others. It is possible that if this station had been operating and configured to alert the EWN, the derailment may have been prevented, or at least the consequences reduced.
While weather monitoring stations were listed as a proposed control within ARTC’s risk registers, the actual effectiveness of the proposed control was likely reduced, as the locations were not selected through a risk-based approach. There was no formal or documented assessment to determine areas of increased risk or susceptibility to extreme weather and flooding. The risk register referred to installing remote weather monitoring equipment at ‘critical points where there is no information from the BoM’, however, ARTC were unable to detail how critical points were assessed.
The EWN had identified existing weather monitoring equipment within 50 km (25 km each side) of the TAR corridor to monitor rainfall. These stations were primarily owned by the BoM and other government agencies and so were not placed for the purpose of detecting weather events that could impact the rail corridor. These stations did however provide an indication of rainfall in an area that could potentially flow towards the corridor. Not all BoM weather stations reported rainfall for frequencies less than 24 hours, which reduced the available data for assessment of shorter periods. Rainfall could have exceeded the 1 and 6 hour ARI for an area but would not have been detected by the EWN or ARTC, if the assessment area relied solely on BoM weather stations.
The lack of additional weather data in the form of weather monitoring stations at locations assessed as critical along the corridor, reduced the effectiveness of ARTC’s weather monitoring procedure to detect extreme rainfall events that exceeded rainfall design limits. The existing BoM stations utilised by the EWN provided limited assurance that rainfall, which could affect the integrity of the rain line, would be detected. None of the weather stations that the EWN monitored recorded rainfall at levels that would have triggered a red or black alert on the night of the occurrence.
Available corridor information at the time that could have highlighted identified risks with hydrology, including flooding and embankments susceptible to overtopping, was not used to inform the locations for installation of weather stations.
ARTC did not have an engineering standard or defined process to assess how or where weather monitoring was required across their network. The risk of rainfall was covered within their ARM procedure, but it did not address the risks associated with heat or wind. There was also no standard or defined process to determine where stream flow detectors were required or would be beneficial as an input to assessing the risk of flooding in the rail corridor.
Flood risk and cross drainage systems
Flooding risk
The Telarah to Acacia Ridge (TAR) corridor crossed many rivers and creeks that were prone to flooding. Some of these rivers and creeks were monitored by the BoM but most were not. Bridges over the larger rivers were reported as typically being designed for 100 ARI flooding. These bridges were less likely to experience flooding when compared to cross drainage[84] structures along the corridor.
Where there was river monitoring equipment (river gauges) the BoM and State Emergency Service (SES) could issue flood warnings for those specific rivers and creeks. More generalised flood warnings issued for other rivers and creeks were based on forecast or observed rainfall. While ARTC did not receive BoM flood warnings from the EWN as expected, they had not assessed the TAR corridor for areas that would be affected by those warnings.
Consequently, rises in river levels that could have affected the integrity of ARTC’s infrastructure may not have been reliably detected by ARTC. Additionally, areas of increased risk had not been assessed. Therefore, ARTC’s awareness of flooding that could have affected the integrity of network infrastructure relied on ARTC personnel to detect flooding through visual inspections or reports from train crew.
Extreme weather risk register
ARTC had a risk register for Extreme weather events that was applicable for the Defined Interstate Rail Network (DIRN). The risk was described as flooding causing damage, washaways and delays, as well as delays due to signal failures. The consequences of this risk were derailment, damage to track and train delays. The causes of these risks were extreme weather (including flooding) and unknown hydrology, and the preventative controls for both causes were:
Inspection
Hydrology reports
Inspect and restore drainage where inadequate - at risk areas from last known occurrence
Risk assess areas likely to be washed out where inadequate or no flood openings
Advice issued to drivers when extreme weather conditions known
Investigation of early warning devices now that could be used because of upgraded data availability
Risk assessment/hydrological surveys conducted for all replacement structures and when incidents are reported
Flood mitigation strategies reviewed or developed as a result of major flooding on a local basis and when required.
While the risk register included a control to inspect and restore drainage where inadequate and undertaking risk assessments for areas likely to be washed out, ARTC did not provide evidence of this being applied along the TAR corridor. It is possible there were some assessments historically to address these risks but evidence of these was not provided.
ARTC advised that they had undertaken some detailed flood assessments at locations with repeated flooding events to determine if additional risk measures were required. Evidence was provided for several studies undertaken for the east-west corridor. The outcome of those studies was the identification of high-risk locations and installation of 30 sets of stream flow monitoring equipment. Similar studies had not been undertaken along the TAR corridor.
Flooding special locations
It was a requirement of ARTC’s Code of Practice Section 10 Flooding, that a register of flooding special locations was established and maintained. While ARTC were aware that the TAR corridor was prone to flooding, they had not established or maintained a flooding special locations register. The Corridor Manager (CM) advised that they treated the entire TAR corridor as a flooding special location, however there was no register to document specific areas prone to flooding or damage.
ARTC had reduced visibility of areas affected by flooding as they had not systematically assessed and documented areas with a history of flooding. If a track patrol or unscheduled inspection was triggered by a defined event (rainfall or stream flow), areas of increased risk may not consistently have been inspected. ARTC was reliant on the memory and local knowledge of their maintenance personnel for areas at increased risk of flooding. This approach could have been inconsistent and or compromised by loss of knowledge with the movement of personnel and fallibility of memory.
A flooding special locations register would have been less effective for areas that had not experienced a flash flood event. However, a register of locations where flash flood events had occurred could have highlighted potential areas to monitor for flooding in the future. Recording of flash flooding events could also have provided an opportunity to assess the effectiveness of weather monitoring equipment and any responses for that area.
Drainage systems
There were a significant number of smaller creeks and rivers that needed to pass under the rail line through culverts along the TAR corridor. Of these, numerous culverts were identified as being at increased risk of overtopping the embankment or having issues with hydrology. Some were identified through the culvert assessment study[85] as far back as 1995 and others were noted in ARTC’s geotechnical database.
The culvert assessment study was completed nine years prior to the rail corridor being leased to ARTC, and evidence could not be found to explain what if anything had been done in response to the study prior to ARTC being granted the lease. While ARTC had a copy of the study and had recorded information in their geotechnical database, they were unable to provide any records that accounted for how the risk of overtopping and washaway was assessed, addressed, or mitigated in the intervening period. ARTC advised that they inspected all culverts in accordance with their Technical Maintenance Plan (TMP) and in line with their safety management system (SMS). Review of ARTC’s asset management system confirmed that the culverts had been inspected, however there was no requirement within their TMP to assess and confirm that the infrastructure was fit for purpose. ARTC were unable to provide any records detailing an assessment of embankment overtopping risk due to culvert capacity or an assessment of hydrology risks along the TAR corridor.
ARTC personnel reported that they treated most existing culverts as having an ARI of less than 20, however, there was no specific requirement to assess the actual capacity. While it was expected that red alerts would be triggered if rainfall exceeded a 20 ARI threshold, alerts would only be generated if there was weather monitoring equipment in the vicinity. However, based on the defined response for a red alert, culverts with capacities of less than 20 ARI may still not have been inspected and flooding could have gone undetected.
While acknowledging the significant number of culverts along the TAR corridor, ARTC had not undertaken assessments to determine locations at most risk of rainfall and flooding events that would exceed culvert design. This reduced the effectiveness of their response to flooding as well as limited the visibility of areas requiring future investment.
Occurrence culvert
The culvert at 643.849 km was known to be at increased risk of overtopping the embankment and washaways since 1995.[86] However, prior to the derailment ARTC did not have any detailed design documents for the culvert and had not undertaken any risk assessments to manage the identified risk.
In 2018, ARTC commissioned a study to assist in determining when it might be safe to re-open their network following a closure from a black alert for the north-south and east-west corridors.[87] To determine this, the study identified the catchments with the longest time of concentration (Tc)[88] for each section of track. The peak discharge for a 100 ARI event was then estimated using the Australian Rainfall and Runoff 1987 data set. A comparison was also performed using the Regional Flood Frequency Estimation (RFFE) Model[89] to validate the estimated the peak discharge.
The culvert at 643.849 km was assessed as being the culvert with the longest Tc for the section of track between 595 km to 877 km. The estimated discharge from the study for the culvert at 643.849 km are shown in Table 13. The upper and lower confidence limits are also shown indicating the potential peak discharges.
Table 13: Culvert 643.849 km peak flow discharge estimates
The RFFE model was used to estimate the peak flows for Cowans Creek based on the revised Australian Rainfall and Runoff data 2016.[90] The peak flow discharge estimates for six different rainfall events over a duration of six hours are shown in Table 14.
Table 14: Regions Flood Frequency Estimates – Cowans Creek – 643.849 km
The estimated peak flow discharges during 50 ARI (2% AEP) and 100 ARI (1% AEP) events (Table 14) as well as those from the 2018 study (Table 13) all exceeded 50 m3/s. As per ARTC’s structures standard, major undertrack drainage structures equalling or exceeding 50m3/s where required to be designed for 100 ARI (1% AEP) flood events. However, this standard was not applied by ARTC to existing structures, nor was it mandatory to apply if replacing existing structures. ARTC advised that when replacing existing structures, they would be assessed on a case-by-case basis using professional judgement and known risk of flooding.
Had the culvert been designed to either a 50 ARI or 100 ARI flood event, overtopping would probably still have occurred, although it probably would have been less severe.
Following the occurrence, no action was taken to increase the capacity of the culvert at 643.849 km. Although a known risk, ARTC did not undertake any risk assessments associated with the culvert capacity before re‑opening the TAR corridor. Post derailment, ARTC commissioned a hydrological study for the area, but it was not finalised as of this final report. To manage the risk until the hydrology study was completed, the area between Coramba and Kungala (640 km to 659 km) was added to their flooding special locations register developed after the derailment. The intent was to prevent rail traffic entering the entire area when rainfall exceeded the rainfall thresholds for that area until it was assessed as safe.
Network Control Centre South fatigue management
In the 14-day period prior to and including the occurrence shift, both the TTM and NCO worked several shifts that were not in accordance with the operator’s fatigue Work Instruction. These shifts were backwards rotating with a minimum of eight hours between some shifts.
There was no evidence available that their work outside of ARTC’s fatigue guidelines was assessed for the likely level of additional risk involved, or appropriate risk control measures identified, or applied.
While rostering of the TTM and NCO did not contribute to the occurrence, ARTC’s network control rostering practices increased the likelihood of persons experiencing fatigue at levels demonstrated to adversely affect safe performance.
Most people need at least 7-8 hours of sleep each day to achieve maximum alertness and performance, with research showing that less than 6 hours sleep can increase risk of fatigue.[91],[92] Research has also shown that sleep of less than 5 hours in the previous 24 hours is inconsistent with a safe system of work.[93] The rostered time free of duty between shifts, of 8 hours, provided a period of sleep opportunity of less than 8 hours, in consideration of travel time, meals and other domestic requirements.
In addition, there was a safety improvement opportunity for defining the risk assessment process, when work was required outside of the ARTC’s fatigue management guidelines, and for ensuring that identified controls were applied and documented.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the derailment of freight train 4BM4 at Nana Glen, New South Wales on 25 February 2021.
Contributing factors
The network users were not aware of the extent of the severe weather event and had not been advised of the amber alert issued prior to the derailment.
The culvert located at 643.849 km did not have sufficient capacity to discharge the runoff from the rain event on the night of 24-25 February 2021. Floodwater built up on the southern side of the embankment before overtopping the track and washing away the ballast at 643.800 km.
The driver of 4BM4 observed water in and around the rail corridor after passing Glenreagh and continued close to track speed (between 60-70 km/h) towards Nana Glen. Water was observed encroaching the rail line and on exiting a right-hand bend, train 4BM4 derailed at a washaway at 643.800 km.
Although ARTC had procedures in place for monitoring and responding to extreme weather events, the process had significant limitations including:
The mechanism (email) for alerting operational personnel required to take action in response to amber alerts did not ensure that alerts were always identified or actioned in a timely manner.
The actions specified for amber and red alerts were insufficient to respond to escalating rainfall and flooding events, both forecast and actual. (Safety issue)
Other factors that increased risk
Neither driver of two previous trains through the section reported a condition affecting the network, relating to the poor weather conditions in the vicinity of Nana Glen, to the network controller. Additionally, although visibility was severely affected, as reported by the drivers, they did not slow the train which reduced their opportunity to sight signals, potential obstructions and safely traverse level crossings.
Neither ARTC or PN provided guidance for train crew to respond to extreme wet weather events or floodwater in the rail corridor. There was no guidance for when trains should stop or report if there was water on the track formation, covering the ballast, sleepers or the rail. (Safety issue)
The culvert at 643.849 km and numerous other culverts along the Mid North Coast had been identified as far back as 1995, as inadequate and susceptible to overtopping which increased the risk of the track structure washing away at those locations.
ARTC could not reliably determine the risk of flooding along the Telarah to Acacia Ridge corridor or the risks associated with inadequate capacity cross drainage systems. (Safety issue)
ARTC had not undertaken formal assessments to determine the need for or the locations of remote weather monitoring stations to detect extreme weather events that could affect the integrity of its rail infrastructure. (Safety issue)
The weather alerts issued by the EWN did not reliably reflect the data and frequency of ARTC’s extreme weather monitoring procedure or the service agreement. This and the services ARTC believed were included in the service agreement likely impacted the expectations of ARTC users who relied on these warnings to inform their response. (Safety issue)
The rostering practices for ARTC’s network control leading up to the occurrence, increased the likelihood of persons experiencing fatigue at levels that have been demonstrated to adversely affect safe performance.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the rail industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: Neither ARTC or PN provided guidance for train crew to respond to extreme wet weather events or floodwater in the rail corridor. There was no guidance for when trains should stop or report if there was water on the track formation, covering the ballast, sleepers or the rail.
Safety Recommendation description: The Australian Transport Safety Bureau recommends that Australian Rail Track Corporation develops guidance for train crew to respond to and report extreme wet weather events or floodwater in the rail corridor.
Safety Recommendation description: The Australian Transport Safety Bureau recommends that Pacific National develops guidance for train crew to respond to and report extreme wet weather events or floodwater in the rail corridor.
Safety issue description:ARTC had not undertaken formal assessments to determine the need for or the locations of remote weather monitoring stations to detect extreme weather events that could affect the integrity of its rail infrastructure.
ARTC and EWN weather monitoring procedure and service agreement
Safety issue description: The weather alerts issued by the EWN did not reliably reflect the data and frequency of ARTC’s extreme weather monitoring procedure or the service agreement. This and the services ARTC believed were included in the service agreement likely impacted the expectations of ARTC users who relied on these warnings to inform their response.
ARTC Extreme Weather Monitoring and Response (Amber and Red Alert)
Safety issue description: Although ARTC had procedures in place for monitoring and responding to extreme weather events, the process had significant limitations including:
The mechanism (email) for alerting operational personnel required to take action in response to amber alerts did not ensure that alerts were always identified or actioned in a timely manner.
The actions specified for amber and red alerts were insufficient to respond to escalating rainfall and flooding events, both forecast and actual.
Safety issue description: ARTC could not reliably determine the risk of flooding along the Telarah to Acacia Ridge corridor or the risks associated with inadequate capacity cross drainage systems.
Safety action not associated with an identified safety issue
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Additional safety action by Early Warning Network (EWN)
The Early Warning Network advised that following the occurrence, they revised their alert generator (software program) for generating and distributing weather alerts to include the phrase 'life threatening flash flooding'. Weather alerts issued by the Bureau of Meteorology that included this phrase would automatically be identified as a red alert and communicated to the EWN's customers including ARTC.
Glossary
AEP
Annual Exceedance Probability: The probability that a given rainfall total accumulated over a given duration will be exceeded in any one year. AEP is usually expressed as a percentage, and common references include 1% AEP and 2% AEP. Source: RISSB AS 7637:2013.
ADH
Australian Height Datum
AIDR
Australian Institute for Disaster Resilience
AM
Area Manager
ARI
Average Recurrence Interval: The average or expected value of the periods between exceedances of a given rainfall total accumulated over a given duration. It is implicit in this definition that the periods between exceedances are generally random. ARI is generally expressed as years, and common references include 1 in 2-year ARI, 1 in 10-year ARI, 1 in 50-year ARI, and 1 in 100-year ARI. Source: RISSB AS 7637:2013.
ARM
Automatic Rainfall Monitoring
ARR
Australian Rainfall and Runoff is a national guideline document, data and software suite that can be used for the estimation of design flood characteristics in Australia.
ARTC
Australian Rail Track Corporation
BFT
Brisbane Freight Terminal
BoM
Bureau of Meteorology
CRIA
Country Rail infrastructure Authority
CM
Corridor Manager
Culvert
The term culvert is normally applied in engineering practice to any large underground pipe especially where used in relatively short lengths to convey streams or floodwater under an embankment or structure.
DIRN
Defined Interstate Rail Network
CCTV
Closed-circuit television
ECL
East Coast Lows
EWG
Extreme Weather Group
EWN
Early Warning Network
FOT
Front of train footage
ha
Hectare (ha) – a surface measurement, a common unit of measure for land in the metric system. 1 ha equals 10,000 square meters or 1 km2
Heavy rainfall
Rainfall over a period between 30 minutes and 6 hours which exceeds the 10% AEP depth (BoM).
HV
Hunter Valley
Intense rainfall
Rainfall over a period between 30 minutes and 6 hours which exceeds the 2% AEP depth (BoM).
IPS
Integrated Planning Services, Pacific National
Low visibility
Any condition that does not allow Competent Workers to view the distance required to work safely (RISSB). Visibility restricted by fog, mist, rain, dust, snow, low light or other similar cause (ARTC glossary).
km
kilometre, a unit of measure equal to 1,000 m
NC
Network Control
NCCN
Network Control Centre North, located at Broadmeadow in New South Wales
NCCS
Network Control Centre South, located at Junee in New South Wales
NCO
Network Control Officer
NSW
New South Wales
ONRSR
The Office of the National Rail Safety Regulator. Administered and enforced compliance with the Rail Safety National Law and Regulations.
PN
Pacific National
QR
Queensland Rail
RAIB
Rail Accident Investigation Branch, United Kingdom
RFFE
Regional Flood Frequency Estimation Model
RIC
Rail Infrastructure Corporation
RIM
Rail infrastructure manager
RISSB
Rail Industry Safety and Standards Board. Responsible for the provision of standards, codes of practice, guidelines, rules, safety data and analysis for the Australian rail industry.
RRV
Road rail vehicle
RSSB
Rail Safety and Standards Board, United Kingdom
RTO
Rail transport operator. Encompassed both rail infrastructure managers (track, signalling etc.) and rolling stock operators (locomotives, wagons etc.).
SDM
Service Delivery Manager
SES
State Emergency Services
SMS
Safety management system. A systematic approach to organisational safety encompassing safety policy and objectives, risk management, safety assurance, safety promotion, third party interfaces, internal investigation and SMS implementation.
SRA
State Rail Authority
t
tonnes, a unit of mass equal to 1000 kilograms
Tc
Time of concentration refers to the time for rainfall that falls at the furthest point in a catchment to flow as runoff to the outlet, in this case the culvert.
TfNSW
Transport for NSW
TTM
Train Transit Manager
UK
United Kingdom
Sources and submissions
Sources of information
The sources of information during the investigation included the:
train crew of 4BM4 and previous trains 3MB4 and NT31
network controller, train transit manager and corridor manager
Australian Rail Track Corporation
Bureau of Meteorology
Early Warning Network
Fire and Rescue NSW
NSW Trains
Office of the National Rail Safety Regulator
Pacific National
Rail Industry Safety Standards Board.
References
Australian Dangerous Goods Code (2020), Australian Code for the Transport of Dangerous Goods by Road & Rail, Edition 7.7.
Keller R and Weeks W (2019), Flood Hydraulics, Book 6, Chapter 3 Hydraulic Structures in Australian Rainfall and Runoff - A Guide to Flood Estimation, Commonwealth of Australia. Accessed at: https://arr.ga.gov.au/arr-guideline
Kellogg Brown & Root Pty Ltd (2018), ARTC Track Closure Timing Assessment - North South and East West Rail, BEW854-TD-WE-REP-0001, Rev. A, 5 July 2018
NSW Trains (2019), NTTWP 100 Responsibility of Train Crew, 24 October 2019
Paterson Consultants Pty Limited (1995), North Coast Line Culvert Assessment, Nana Glen to Glenreagh, Gurranang to Lawrence Road.
Rail Industry Safety and Standards Board (2013), AS 7367:2013, Railway Structures
Rail Industry Safety and Standards Board (2014), ANRP 2027 Responsibilities of Rail Traffic Crews, V1.2, 10 June 2014
Rail Safety and Standards Board (2020), GERT8000-M3 Rule Book, Managing incidents, floods and snow, Issue 3.1, 5 December 2020
Thomas MJW and Ferguson SA (2010), Prior sleep, prior wake, and crew performance during normal flight operations, Aviation, Space, and Environmental Medicine, vol. 81, pp. 665–670.
Tsubaki R, Bricker J, Ichhii K, and Kawahara Y (2016), Development of fragility curves for railway embankment and ballast scour due to overtopping flood flow, National Hazards and Earth Systems Science, 16, 2455–2472, 2016.
Williamson A, Lombardi DA, Folkard S, Stutts J, Courtney TK & Connor JL (2011), The link between fatigue and safety, Accident Analysis and Prevention, vol. 43, pp. 498–515.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
train crew of 4BM4 and previous trains 3MB4 and NT31
network controller, train transit manager and corridor manager
Australian Rail Track Corporation
Early Warning Network
NSW Trains
Office of the National Rail Safety Regulator
Pacific National.
Submissions were received from:
Australian Rail Track Corporation
Early Warning Network
Office of the National Rail Safety Regulator
Pacific National.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Appendices
Appendix A – OPE-PR-014 response tables and Appendix B – ARTC and EWN rainfall monitoring areas are detailed in the attached PDF copy of this report.
Appendix C – Culvert concepts
Culverts
Culverts are a hydraulic structure used to convey water under an embankment or other similar earthen structure. The shape of a culvert can be circular, square, arch and can be made of different materials. Culverts are usually laid on a slope to facilitate the flow of water and reduce sedimentation within the culvert.
Control method
Culverts will always be operating in one of two conditions, either inlet or outlet control. The control point can change during operation and can be difficult to predict. A culvert flowing full through its length will always be in outlet control, while a culvert flowing part full can be either inlet or outlet control.
When in inlet control the discharge only depends on the elevation of the headwater above the entrance (invert), and the inlet size and geometry. The length, slope and roughness of the pipe wall do not affect the discharge of the culvert. The discharge velocities can be high when operating under inlet control.
Culverts operating in outlet control are affected by all factors upstream of the outlet. These include the headwater elevation, entrance geometry, and the barrel size, length and slope. Tailwater is also a factor if it is above the elevation of the pipe outlet. With high tailwater, the outlet velocity can be low and high headwater can be an issue.[94],[95] High tailwater alone is capable of making a culvert operate under outlet control, when it would otherwise be under inlet control.[96]
With the rise in the Orara River the culvert would probably have been operating in outlet control. Once the tailwater passes above the height of the outlet, any change in the height of the tailwater (Orara River) would be reflected on the upstream headwater at one-to-one ratio.
Inlet and outlet structures
For culvert inlet and outlet structures, headwalls (endwalls) and wingwalls of reinforced concrete are usually needed to provide embankment stability and protection against erosion. Culverts with wingwalls should be designed with an apron extending between the walls. The actual configuration of the wingwalls will vary according to the direction of flow and so protection against scour is maximised through inclusion of the apron.[97]
Headwall (endwall) – The endwall structure alone acts to support the end of the culvert and as a retaining wall for the embankment.
Wingwall – Wingwall directs the water into the pipe and helps to transition the culvert flow smoothly into the downstream channel and protects the endwall so that it may continue to function in its original capacity.
Blockages
Culverts can be susceptible to blockages which can impact flood levels, change erosions and deposition patterns in channels, and physical damage to the structure.
The factors that can influence blockages include the location of the catchment and availability and type of debris. Leaves and branches can cause blockages very quickly. In larger culverts, rubble or debris can cause an issue. Blockages involving floating debris may arrive or build up as a floating raft that rises with the floodwater and is only deposited over the inlet. Sometimes mud, silt or other natural detritus can build up over time.[98]
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Time shown as 24-hour time as Australian Eastern Standard Time (AEST).
[2] Times shown in 24-hour time as Australian Eastern Daylight Time (AEDT) for the remainder of this report.
[3] The Up direction refers to the direction of travel for trains heading towards Sydney. The Down direction refers to trains heading away from Sydney.
[4] Roll-by inspections were a visual inspection of moving rail traffic to identify equipment, loading security or other defects or failure.
[5] Scour: The removal of soil and rocks around a structure though erosion.
[6] Formation: The full width of the top of embankments or the bottom of cuttings upon which the track is constructed. Refer to Figure 21 for graphical representation.
[7] The Defined Interstate was the standard gauge interstate rail line linking the mainland capital cities (except Darwin) and the regional centres of Alice Springs, Darwin, Whyalla, Port Kembla and Newcastle.
[8] The original lease was between the State Rail Authority (SRA), Rail Infrastructure Corporation (RIC) and Australian Rail Track Corporation. In 2007, the assets held or owned by SRA were transferred to RIC. RIC was rebranded in 2010 as Country Rail Infrastructure Authority (CRIA). In 2012 the CRIA was abolished and control of all regional assets, rights and liabilities were transferred to Transport for NSW (TfNSW).
[9] An NSW Government agency constituted by the Transport Administration Act 1988 Part 1A Section 3C.
[10] East Coast Lows (ECL) are intense low pressure systems which occur, on average, several times each year off the eastern coast of Australia, in particular southern Queensland, NSW and eastern Victoria. Although they can occur at any time of the year, they are more common during autumn and winter with a maximum frequency in June. East Coast Lows will often intensify rapidly over a period of 12-24 hours making them one of the more dangerous weather systems to affect the eastern coast. Source: BoM
[11] The river height gauge at Glenreagh had recorded moderate flooding (9 m) on 31 occasions between 1972 and February 2021. Of those, 16 moderate floods were recorded between 2007 and 2021. Major flooding exceeding 13 m was also recorded in 2009 and 2013.
[12] An articulated wagon comprising five platforms, the adjacent ends of individual units being supported on a common bogie and permanently connected by a device which permits free rotation in all planes. Note, these do not always consist of five units; they could be 2-packs, 3-packs etc.
[13] Australian Dangerous Goods Code (2020), Australian Code for the Transport of Dangerous Goods by Road & Rail, Edition 7.7. The code details the classification and designation of dangerous goods, including the allocation of UN numbers.
[14] The environmentally hazardous substance designation was for substances and mixtures which were dangerous to aquatic environments.
[15] N.O.S: not otherwise specified (N.O.S) is the designation for substances not specified elsewhere as per the Australian Dangerous Goods Codes.
[16] NT31 consisted of the following carriages, XP2013 (leading), XAM2178, XL2230, XBR2152, XF2203, XF2220, XFH2106 and XP2004 (trailing).
[17] Refer to Condition affecting the network on page 44.
[18] Cess: the area between the outermost rail and the boundary of the rail corridor.
[19] Amber refers to ARTC’s classification of the risk associated with the weather. See Weather monitoring and response on page 37 and Table 9 for further details relating to the colour coding of weather alerts.
[20] Flash flooding: flooding occurring within about six hours of rain, usually the result of intense local rain and characterised by rapid rises in water-levels.
[21] The Bureau of Meteorology classified intense rainfall as rainfall over a period between 30 minutes and 6 hours which exceeds the 2 per cent Annual Exceedance Probability (AEP) depth. Heavy rainfall was classified as rainfall over a period between 30 minutes and 6 hours which exceeds the 10 per cent AEP depth.
[22] Recorded at the Nana Glen (Cowling Close, Station ID 059139) weather station which was located 1.59 km west of the derailment site on the opposite side of the Orara River.
[23] Glenreagh Bridge river monitoring equipment (BoM Id: 559066) was 6.48 km north west of the derailment site.
[24] River height gauges at Orange Grove (BoM Id: 559018) was 17.05 km south-south west from the derailment site and Karangi (BoM Id: 559023) was 16.56 km south of the derailment site (Figure 12).
[25] The BoM Weather Watch radars were effective for the detection of rain. These radars could be used by forecasters to interpret the patterns and intensity of the radar images, to provide warnings of major weather events such as severe thunderstorms and areas of heavy rainfall. The radar images showed the location of rain in relation to local features such as the coastline, with different colours used to depict rainfall intensity.
[26] La Niña events increase the chances of above-average rainfall for northern and eastern Australia during spring and summer. The La Niña is influenced by the trade winds and water temperatures of the Pacific Ocean and are of the El Niño Southern Oscillation (ENSO). ENSO is the oscillation between El Niño and La Niña conditions. While La Niña will typically result in above average rainfall the El Niño with typically result in below average rainfall.
[28] NSW Office of Environment and Heritage (2014), North Coast Climate change snapshot
[29] Bureau of Meteorology and CSIRO (2020), State of the Climate 2020
[30] Rail Vehicle Detection (RVD): the portions of line where the system of safeworking relies on track circuiting or axle counters.
[31] Australian Rail Track Corporation (2018), WHS-WI-423 Fatigue, Work Instruction, V4.1, 14 March 2018
[32] Australian Rail Track Corporation (2011), Code of Practice, Flooding, Section 10, V2.2, 8 November 2011
[33] Waterway: A channel or stream. In relation to hydraulic structures, the area available for water to pass through or under a structure.
[34] Australian Standard AS 5100:2017, Bridge Design – Parts 1 to 9
[35] Rail Industry Safety Standards Board (2013), AS 7367:2013, Railway Structures, and Australian Rail Track Corporation (2013), RTS 3433, Track Drainage – Design and Construction, Issue A, Revision 1, 6 June 2013
[36] Flood Immunity: A measure of the protection provided to infrastructure for a certain flood event (i.e. a bridge that is considered to be immune to a 100-year ARI flood is predicted to not be overtopped during this event).
[37] Overtopping: The rising of water over the top of a structure.
[38] Australian Rail Track Corporation (2019), Code of Practice, Structures, Section 9, V3.7, 31 January 2019
[39] Annual Exceedance probability (AEP): the probability of a rainfall event being equalled or exceeded within a year.
[40] Average Recurrence Interval (ARI): the average time period between occurrences equalling or exceeding a given value.
[41] Australian Standard AS 5100:2017, Bridge Design – Parts 1 to 9
[42] Australian Rail Track Corporation (2019), Structures Inspection, ETE-09-01, V2.6, 20 August 2019
[43] Australian Rail Track Corporation (2021), Civil Technical Maintenance Plan, ETE-00-03, V4.3, 27 October 2021
[44] Invert refers to lowest interior level or floor of a culvert, trench or tunnel. The obvert refers to the highest interior level or ceiling.
[45] Elevations referenced to the Australian Datum Height (ADH).
[46] Catchment: the land area draining to a point of interest, such as a water storage or monitoring site on a watercourse.
[47] GHD Pty Ltd for Coffs Harbour City Council (2012), Final Report Orara River Flood Study, Section 1-10, p 21.
[48] GHD Pty Ltd for Coffs Harbour City Council (2012), Final Report Orara River Flood Study, Section 1-10.
[49] Paterson Consultants Pty Limited (1995), North Coast Line Culvert Assessment, Nana Glen to Glenreagh, Gurranang to Lawrence Road.
[50] Freeboard: The difference in height between the calculated water surface elevation and the top, obvert, crest of a structure or the floor level of a building, and provided for the purpose of ensuring a safety margin above the calculated design water elevation.
[51] Waste ash from locomotive boilers was historically used as fill material to repair embankments.
[52] Australian Rail Track Corporation (2014), Monitoring and Responding to Extreme Weather Events in the East-West Corridor, OPP-01-05, V1.0, 29 May 2014
[53] East-west corridor for the purpose of the procedure was between Cootamundra, NSW and Kalgoorlie, Western Australia.
[54] Extreme weather event: any event including but not limited to floods, electrical storms, and damaging winds which demonstrate potential to impact on the ARTC rail network or the organisation’s operations.
[55] Intensity-Frequency-Duration (IFD): rainfall intensity (mm/h) or design rainfall depths (mm) are based on statistical analysis of historical rainfall events with a corresponding probability of the rainfall event occurring. The IFDs are used for designing infrastructure such as culverts, storm water drains and flood mitigation but can also be used to assess the severity of observed rainfall.
[56] The east-west corridor for the purpose of the procedure was Cootamundra to Broken Hill (NSW), Broken Hill to Peterborough (South Australia), Peterborough to Pimba, Pimba to Oodlea, Oodlea to Rawlinna (Western Australia), and Rawlinna to Kalgoorlie.
[57] Australian Rail Track Corporation (2017), Monitoring and Responding to Extreme Weather Events, OPE-PR-014, V3.0, 15 August 2017
[58] Australian Rail Track Corporation (2019), Monitoring and Responding to Extreme Weather Events, OPE-PR-014, V3.4, June 2019
[59] Train crew were not considered as ‘network users’ as part of the process of the TTM advising network users and operators.
[60] Bureau of Meteorology Design Rainfall Data System (2016) Australian Rainfall and Runoff - 2016 Design rainfalls
[61] Australian Rail Track Corporation (2020), Consultancy Services Agreement, CA-SA-06312-00, Early Weather Warning Alerts, 21 August 2020.
[62] Australian Rail Track Corporation (2010), Automatic Rainfall Monitoring, ETD-10-01, V1.1, 18 June 2010
[63] The remote weather monitoring stations that were being installed were the Davis, Vantage Pro 2 system.
[64] Australian Rail Track Corporation (2020), ANGE 206 Reporting and Responding to a Condition Affecting the Network (CAN), V3.2, 23 February 2020
[65] Competent worker: a worker certified as competent to carry out the relevant task.
[66] Australian Rail Track Corporation (2017), ANGE 232 Responsibilities of Rail Traffic Crews (Train Crews and Track Vehicle Crews), V3.1, 22 October 2017
[67] NSW Trains (2019), NTTWP 100 Responsibility of Train Crew, 24 October 2019
[68] The Professional Driver Guide provided further information for the safe operation of trains including, defensive driving and driving principals, risk associated with the route, signal and distractions.
[69] Rail Industry Safety and Standards Board (2014), ANRP 2027 Responsibilities of Rail Traffic Crews, V1.2, 10 June 2014
[70] ATSB Transport Safety Report, Rail Occurrence Investigation RO-2018-007, Collision with floodwater involving freight train 6792 Little Banyan Creek, Queensland, on 7 March 2018. Report issued 30 June 2020. Available at www.atsb.gov.au
[75] Controlled speed: a speed that allows rail traffic to stop short of an obstruction within half the distance of clear line that is visible ahead.
[76] The high-speed train was a Class 43 diesel-electric locomotive passenger train which was the design the XPT passenger train was based on.
[77] Paterson Consultants Pty Limited (1995), North Coast Line Culvert Assessment, Nana Glen to Glenreagh, Gurranang to Lawrence Road.
[78] Headwater: the water on the upstream side of a hydraulic structure, in this case a culvert.
[79] Tsubaki R, et al (2016), Development of fragility curves for railway embankment and ballast scour due to overtopping flood flow
[80] Tailwater: the water downstream of a hydraulic structure. Tailwater includes oceans, rivers, creeks, lakes and basins, and can either be considered as steady state or varying over time.
[81] Austroads (2018), Guide to Road Design Part 5B: Drainage – Open Channels, Culverts and Floodways, edition 1.1, August 2018.
[82] The Boyles Bridge (Corindi River) rainfall gauge was owned by Coffs Harbour City Council and was located 12.22 km north east of the derailment site. The gauge reported hourly rainfall data which when working was available on the Bureau of Meteorology’s website.
[83] Along the Telarah to Acacia Ridge (TAR) corridor there were provisioning centres (infrastructure maintenance depots) at Taree, Coffs Harbour and Casino.
[84] Cross drainage: a system of pipes or culverts which conveys storm flows transversely across or under a railway.
[85] Paterson Consultants Pty Limited (1995), North Coast Line Culvert Assessment, Nana Glen to Glenreagh, Gurranang to Lawrence Road.
[87] Kellogg Brown & Root Pty Ltd (2018), ARTC Track Closure Timing Assessment - North South and East West Rail, BEW854-TD-WE-REP-0001, Rev. A, 5 July 2018
[88] Time of concentration: the time for rainfall that falls at the furthest point in a catchment to flow as runoff to the outlet, in this case the culvert.
[89] The Regional Flood Frequency Estimation Model allowed for the estimation of peak discharges for ungauged catchments. The model had a number of limitations and could not be utilised for all catchment types or areas.
[90] Bureau of Meteorology Design Rainfall Data System (2016) Australian Rainfall and Runoff - 2016 Design rainfalls
[91] Thomas MJW and Ferguson SA (2010), Prior sleep, prior wake, and crew performance during normal flight operations, Aviation, Space, and Environmental Medicine, vol. 81, pp. 665–670.
[92] Williamson A, et al (2011), The link between fatigue and safety, Accident Analysis and Prevention, vol. 43, pp. 498–515.
[93] Dawson D and McCulloch K (2005), Managing fatigue: It’s about sleep, Sleep Medicine Reviews, vol. 9, pp. 365–380.
[94] Keller R and Weeks W (2019), Flood Hydraulics, Book 6, Chapter 3 Hydraulic Structures in Australian Rainfall and Runoff - A Guide to Flood Estimation, Commonwealth of Australia.
[95] Austroads (2018), Guide to Road Design Part 5B: Drainage – Open Channels, Culverts and Floodways, edition 1.1, August 2018.
[96] Federal Highway Administration (2012), Hydraulic Design Series Number 5, FHWA-HIF-12-026 HDS 5, U.S. Department of Transportation.
[97] Department of Transport and Main Roads (2019), Manual Road Drainage, Chapter 9 Culvert Design. Queensland Government
[98] Rigby T and Weeks W (2019), Flood Hydraulics, Book 6, Chapter 6 Blockage of Hydraulic Structures in Australian Rainfall and Runoff - A Guide to Flood Estimation, Commonwealth of Australia.
On 3 February 2021, a Robinson Helicopter Company R44 Clipper II helicopter, registered VH‑SXC, was operated by GSL Group Pty Ltd on a passenger charter flight from Proserpine Airport to Whitehaven Beach, Queensland. On board were the pilot and 2 passengers.
While cruising at 1,500 ft between Long Island and Hamilton Island, the pilot smelled burning rubber and saw the clutch warning light flicker briefly. The pilot then heard a bang from behind the cabin, and the clutch warning light illuminated and remained on. The pilot turned the helicopter back toward Long Island, declared an emergency to Hamilton Island air traffic control, and made a successful emergency landing on the beach on the western side of Long Island. The pilot and passengers were uninjured. There was minimal damage to the helicopter.
What the ATSB found
Of the 4 drive belts in the helicopter’s drive system, it was found that the forward 2 drive belts had dislodged and moved forward of the upper sheave. They then lodged against the sheave and clutch shaft, leading to damage to the drive belts and surrounding components.
The other 2 drive belts remained intact and shifted forward from their original sheave positions and were not effectively engaged within the grooves of the sheaves. Consequently, there was a complete loss of effective drive of the rotor system.
In consultation with the Robinson Helicopter Company (RHC), it was found that the previous procedure of extending the clutch actuator to stretch a new drive belt set, was no longer advised. This procedure, which had been carried out on VH-SXC, was performed with the engine stopped and the actuator extended, to hold the drive belts under tension for an unspecified time. RHC identified that if performed regularly, this may lead to overstretching and looseness in the drive belts during start-up. This in turn can result in the drive belts dropping below the lower sheave grooves and misaligning during start-up belt tensioning.
What has been done as a result
RHC has amended the Pilot’s Operating Handbook Safety Notice SN-33 ‘Drive Belt Slack’. This safety notice covers the pre-flight inspection requirements of the drive belts and the rotor turning time after clutch engagement.
RHC recognised that the practice of stretching the drive belts with the clutch actuator engaged was contributing to excessive slack in drive belts at start-up. The procedure of stretching new drive belts by extending the clutch actuator and leaving it engaged with the engine off, has been removed.
The helicopter maintenance organisation has raised awareness with their engineers and advised their customers and operators of the removal of the RHC drive belt stretching procedure. They have also reiterated the requirement for the main rotor blades to be turning within 5 seconds of clutch engagement, and to seek maintenance support if not within these limits.
Safety message
Following the helicopter manufacturer’s latest advice, operators should not stretch new drive belt sets using the clutch actuator. This will avoid overstretching and reduce instances of excessive slackness of the drive belts at start-up and the risk of misalignment.
The outcome highlights the importance of managing an in-flight emergency efficiently by following flight manual emergency procedures and having a pre-planned course of action. These fundamentals enabled the pilot to make a safe landing with no injuries or loss of the helicopter.
The investigation
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 3 February 2021 at about 1240 local time, a Robinson Helicopter Company (RHC) R44 Clipper II helicopter, registered VH‑SXC and operated by GSL Group Pty Ltd, departed Proserpine Airport, Queensland. On board were a pilot and 2 passengers. The passenger charter flight was to visit Whitehaven Beach located on the eastern side of Whitsunday Island (Figure 1). Weather conditions at the time were fine, with clear skies and a 10-15 kt wind from the south-east.
The helicopter departed Proserpine Airport and tracked east over Conway Beach, toward the southern end of Long Island. The flight was to continue to the north of Hamilton Island and then traverse the southern side of Whitsunday Island.
Figure 1: Area of operation
Source: Google Earth, annotated by the ATSB
At about 1255 (15 minutes after departure) while approaching Pine Island at an altitude of 1,500 ft, the pilot identified the smell of burning rubber and observed the clutch actuator light momentarily flicker[1]. The pilot then reported hearing what sounded like ‘a rubber band smacking against the cowling’ from the rear of the cabin and saw the clutch light illuminate and remain on. The pilot also identified a rise in engine RPM, which was controlled by manipulating the throttle, and a slow reduction in main rotor RPM.
In response, the pilot lowered the collective[2] to maintain adequate main rotor speed and turned back toward a resort on the south-west side of Long Island. The pilot also made an emergency radio call to Hamilton Island air traffic control (ATC) detailing the developing situation. Approaching a beach near the resort, the pilot armed the emergency float system in preparation for a potential water landing. In response to the warning light, the pilot pulled the clutch circuit breaker as required by the R44 Pilot’s Operating Handbook (POH) (See the section titled Clutch caution light). The pilot noted the alternator light had also illuminated during the incident.
After conducting an emergency autorotation and landing on the beach, the pilot shut down the helicopter and evacuated the passengers to the front of the helicopter. The pilot advised ATC of the safe landing, and then moved both passengers away to the nearby resort facilities. During the operator’s subsequent inspection of the helicopter, the drive system was found to be damaged.
Photographs taken onsite following the event, showed the forward 2 drive belts had dislodged and shifted out of position from the upper and lower sheaves during operation (Figure 2). There was substantial damage to those drive belts. The images also showed a large amount of rubber dust in the area of the upper sheave, indicating the system had continued to operate while abrading the drive belts after they had dislodged.
The other 2 drive belts remained intact and on the upper and lower sheaves but had shifted forward from their original positions. As that occurred, it led to a loss of effective drive to the rotor system, resulting in the observed rise in engine RPM and a reduction in main rotor RPM.
Several other components were also damaged, these included the:
alternator belt, which was dislodged by the drive belts
oil cooler and oil supply line
lower sheave
fan shaft and bearing
clutch actuator.
Figure 2: Drive system of VH-SXC showing the rear two drive belts remaining on the upper and lower sheaves
Source: Operator photo, annotated by the ATSB
Context
Pilot information
The pilot held a valid commercial pilot licence for both helicopters and aeroplanes, and a current Class 1 aviation medical certificate. They were endorsed on several single and twin-engine, piston and turbine helicopters, including the Robinson R44 (R44).
At the time of the incident, they had about 3,600 flight hours experience, of which about 1,100 hours were in the R44. They completed their last flight review in December 2020, which included emergency autorotation procedures.
Helicopter information
The R44 is a 4-place helicopter that is primarily all metal construction with a 2-blade main and tail rotor system and powered by a 6-cylinder Lycoming piston engine. The Clipper II version of the R44 is fitted with an emergency pop-out float system.
VH-SXC was manufactured in the United States in 2019 and issued serial number 14285. It was initially imported to New Zealand in 2019, before being imported and registered in Australia, in the same year. The maintenance release indicated that VH-SXC had accumulated a total of 461.8 hours in service at the time of the occurrence.
Rotor drive system
The rotor drive on the Robinson R44 helicopter uses 4 reinforced rubber drive belts that engage with upper and lower multi-grooved sheaves. The lower sheave is mounted to the engine crankshaft and the upper sheave is mounted on a free-wheel clutch shaft that drives the main and tail rotor driveshafts.
When engaged, the clutch actuator extends and moves the upper sheave upwards a small amount, which applies tension to the drive belts, transmitting engine power to the rotors (Figure 3). When the drive belts are properly tensioned, the clutch actuator senses the compressive load (drive belt tension), and the clutch actuator switches off.
Figure 3: Robinson R44 rotor drive system
Source: Robinson Helicopter Company, annotated by the ATSB
During engine start, the drive belts are not under tension to reduce the load on the starter motor that would otherwise attempt to turn both the engine and the entire rotor system. After start, the pilot selects the clutch actuator to ENGAGE, tensioning the drive belts within the sheave grooves. The POH stated, that after engaging the clutch actuator switch, the rotors should be turning within 5 seconds. Also, Safety Notice SN-33, Drive Belt Slack states that if:
…rotor does not turn within 5 seconds, shut down and have actuator adjusted prior to flight.
The actuator may operate momentarily during flight as the drive belts warm up or stretch slightly. A caution light illuminates on the instrument panel to indicate any movement of the actuator and a momentary flicker during operation is considered normal.
Clutch caution light
The POH provided advice for the pilot with how to respond to a clutch caution light illumination which has occurred for greater than 10 seconds (clutch motor engaging or disengaging). The response requires the clutch circuit breaker to be pulled, therefore isolating power to the clutch motor. The advice notes:
Clutch light may come on momentarily during run-up or during flight to re-tension belts as they warm-up and stretch slightly. If, however, the light flickers or comes on in flight and does not go out within 10 seconds, pull CLUTCH circuit breaker and land as soon as practical. Reduce power and land immediately if there are other indications of drive system failure (be prepared to enter autorotation). Have drive system inspected for a possible malfunction.
VH-SXC operational and maintenance history
VH-SXC was previously utilised for flight training and, in April 2020 was involved in a dynamic rollover[3] accident which led to substantial damage of the helicopter[4]. The rebuild of the helicopter was consistent with the completion of the R44 2,200-hour overhaul[5] requirements and the 4,400‑hour component replacement schedules. The rebuild included the fitting of new drive belts, clutch shaft and actuator, tail cone and all drivetrain components.
Additionally, during the rebuild, repairs were carried out on the left and right lower frames in accordance with an approved engineering order[6]. Post-assembly alignment checks were performed on the airframe, engine, and drivetrain assemblies. These included adjustments of the sheaves, to ensure proper alignment of the drive belts from the engine lower sheave to the upper sheave. Post-rebuild rigging checks ensured there was no misalignment - a known contributor to drive belts disengaging during operation.
Since the rebuild, but prior to this occurrence, engineers had replaced the drive belts due to overstretching and looseness. Maintenance records showed that the sheave alignment was checked at that service. The drive belts fitted at that time are the subject of this report and failed after only 6.2 hours of flight. Table 1 details the history of drive belt replacement on VH-SXC.
While installing new drive belts following this occurrence, the sheave alignment was again checked, and maintenance records showed that the sheave alignment was stable, changing only 1 thousandth of an inch between drive belt sets. That replacement set of belts were themselves subsequently replaced on 15 February 2021, after only 8.6 flight hours due to overstretching.
Table 1: VH-SXC drive belt maintenance history
Date
Maintenance
Time in service
Notes
23 Apr. 2020
379.5
Dynamic rollover during hover taxi and collision with terrain. Helicopter was substantially damaged.
23 Nov. 2020
Helicopter rebuild carried out
379.5
New drive components fitted include new drive belt set, clutch shaft, and upper and lower sheaves. Sheave alignment carried out.
29 Jan. 2021
100-hour inspection carried out
455.6
Overstretched drive belt set replaced with a new drive belt set. Sheave alignment carried out. Drive belts flight time in service: 76.1 hours.
3 Feb. 2021
Incident flight
461.8
Drive belts disengaged from sheaves in flight leading to emergency landing. New drive belt set, lower sheave, clutch actuator, and alternator belt fitted. Sheave alignment carried out. Drive belts flight time in service: 6.2 hours.
15 Feb. 2021 (post‑incident)
Drive belt set replaced
470.4
Stretched and disengaged drive belt set replaced with a new drive belt set. Sheave alignment carried out. Drive belts flight time in service: 8.6 hours.
Source: VH-SXC maintenance logbook
Drive belt replacement and stretching
The maintenance manual task for the installation of a new drive belt set did not contain a procedure for drive belt stretching or checking drive belt tension. As the drive belts contain rubber, they warm and stretch during use. After shutting down, some drive belts shrink to a minimal slack condition as they cool. This can lead to increased drive belt tension and place additional load on the drive train during start-up.
To remedy this, the POH contained a procedure in Safety Notice SN‑33 (Appendix A) which specified a drive belt stretching procedure using the clutch actuator. The actuator would be engaged, with the engine stopped, and left in this condition for a period[7]. The clutch would then be disengaged during the next pre-flight. Robinson’s reason for this was to limit dimensional reductions that could occur as the drive belts cooled. Robinson further advised that this procedure was intended to be used as a one-off procedure, and then further adjustments to belt engagement time was to be done through adjustment of the clutch actuator down-limit switch. However, these details were not included in the safety notice.
The procedure for stretching the drive belts in service was listed only in the POH due to these characteristics of the drive belts. If the pilot determined that the drive belts were too tight, they could perform the stretching, without the need for maintenance personnel to be involved.
The maintenance organisation advised that the procedure for static stretching of the drive belt set as described in SN-33 was used for each set of new drive belts fitted to VH-SXC at the initial installation. Additional stretching of the drive belts was then performed by the operator, for a further 5 flight hours. This was conducted in accordance with SN-33, under the guidance from the maintenance organisation, with the clutch remaining engaged overnight.
Drive belt examination
The drive belt set was examined at the ATSB’s technical facilities in Canberra (Appendix B). The examination found that the 2 forward drive belts had dislodged, leading to substantial damage to the drive belts. The drive belts had also been damaged by the rotating drive system components, causing rubber to be abraded from the drive belts and a vee section of each drive belt to be torn free.
Both rear drive belts had remained on the upper and lower sheaves but had moved forward from their original locations and not engaged in the sheave grooves. The drive belt set was measured, and the rear drive belts had stretched about 40 mm greater in diameter when compared with the forward drive belts. This indicated that the rear drive belts had continued to operate after the forward drive belts had dislodged and were stretched by the extension of the clutch actuator.
Safety analysis
Repeated drive belt loss
Repairs to the helicopter had been performed according to applicable manufacturer’s instructions and engineering orders. The stability of the sheave alignment from rebuild, and between drive belt sets replacements, indicate that this was not the source of drive system failure.
The drive belt stretching procedure, which was current at the time and recommended by the manufacturer, was used on each set of drive belts, and for an additional 5 flight hours thereafter to remedy the tight drive belts. However, the procedure of engaging the clutch actuator as a means of stretching tight drive belt sets was later recognised by Robinson Helicopter Company as a contributing factor to excessive slack in the drive belts at start-up.
Robinson’s intent of the procedure in SN-33 was that the stretching of the drive belts was to be a once only application. However, this was not detailed in the safety notice and in-service feedback from operators showed it was being performed multiple times. It is likely that the multiple use of the stretching process contributed to the repositioning of the drive belts in operation.
Pilot response
In dealing with emergencies pilots follow a basic set of priorities: aviate, navigate, and communicate. Once the pilot of VH-SXC diagnosed a problem within the drive train, they reacted to the increasing engine speed and decreasing rotor speed by following the POH procedure and maintained control of the helicopter.
The pilot also followed the POH procedure for isolating power to the clutch by pulling the clutch circuit breaker following the steady illumination of the clutch warning light. On this occasion, had the circuit breaker for the clutch not been pulled, the remaining two rotor drive belts may have tensioned and restored drive to the rotor system. However, faced with the burning rubber smell, clutch light illumination and banging sound and no way to visually assess the drive belt condition, the pilot’s actions were prudent.
They then conducted an immediate return and navigated toward Long Island to a suitable landing location, before communicating their situation and intentions to Hamilton Island control tower.
Observing this fundamental approach and using the POH procedures allowed the pilot to have a clear decision-making process and procedure to achieve a safe outcome.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the drive system failure and forced landing, involving a Robinson Helicopter Company R44 II, VH-SXC 11 km west of Hamilton Island, Queensland on 3 February 2021.
Contributing factors
The drive belt stretching procedure current at the time of the occurrence was used, and likely overstretched the drive belts, permitting the drive belt set to become misaligned upon tensioning of the system.
The 2 forward drive belts displaced from the upper and lower sheaves and became entrapped against the rotating components, leading to abrading of the drive belts. The load on the remaining rear 2 drive belts led to them moving forward and disrupting the rotor system drive, necessitating a forced landing.
Other findings
In responding to the situation, the pilot carried out an emergency landing on a nearby island resulting in minimal damage to the helicopter and no injuries to the pilot or passengers.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Safety action by Robinson Helicopter Company
Robinson Helicopter Company (RHC) identified that the procedure utilising the clutch actuator to statically stretch the drive belts was a likely cause of excessive slack in the drive belts at start-up.
In July 2021, 5 months after this event, RHC proactively removed the drive belt stretching procedure from the safety notice contained in the pilot’s operating handbook, The amended page was published on the Robinson Helicopter Company website, and has likewise been updated for the R22.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot of VH-SXC
operator
maintenance provider
Robinson Helicopter Company
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the pilot of VH-SXC
the operator
the maintenance provider
the Civil Aviation Safety Authority
Robinson Helicopter Company.
Submissions on that draft report were received from the:
operator
maintenance provider
Robinson Helicopter Company
Civil Aviation Safety Authority.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly. Given the nature of the amendments, a second draft was provided to the following directly involved parties:
the pilot of VH-SXC
the operator
the maintenance provider
Robinson Helicopter Company.
Submissions on the second draft report were received from the:
operator
Robinson Helicopter Company
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
References
Australian Transport Safety Bureau, 2013, Reliability of the Robinson R22 helicopter belt drive system, AI-2009-038, Canberra, ACT
Robinson Helicopter Company 2020, R44 Pilot’s Operating Handbook, section 4, p.4-3 and section 10, p.26 Safety Notice SN-33.
The drive belt set from VH-SXC was sent to the ATSB’s technical facilities in Canberra for examination. For reference purposes, the drive belts were marked by the Robinson Helicopter Company (RHC) A through D. Belt A is the forward drive belt and belt D is at the rear of the drive belt set. The set is also marked by RHC with a painted arrow marking, which ensures that the drive belt set is installed in the same order each time they are removed.
The ATSB examination found that the drive belts contained 2 differing part numbers (PN). The forward drive belt was PN A190-3, while the rear 3 drive belts were identified as PN A190-2. All 4 drive belts were Revision (Rev) AB. Although the drive belts were marked with part numbers that applied to both the R44 and R22 helicopter type, the markings from manufacture indicated they were supplied as a matched set from the RHC factory (Figure 4).
Figure 6: Drive belt set removed from VH-SXC
Source: ATSB
RHC reported that the A190-2 Rev AB drive belts possess the same dimensions and characteristics as the A190-3 Rev AB drive belt. When the R22 reverted to the Rev Z drive belt, a significant number of A190‑2 Rev AB drive belts were re-measured, matched as a set and re‑identified as A190-3 Rev AB and categorised as an R44 drive belt set. The drive belt set removed from VH-SXC had the additional markings of a part numbered set of A190-3 AB, consistent with the information supplied by the manufacturer, confirming the correct part was fitted to the helicopter (Figure 5).
Figure 7: Drive belt set part number
Source: ATSB
All 4 drive belts appeared to be of a similar construction with 11 tensile cords contained within each ‘vee’. Figure 6 shows drive belt A, which had sustained significant loss in overall width and the rear part of the vee torn from the tie band. Belt B was similarly damaged, having the forward vee torn form the tie band. The intact drive belts, C and D, were of larger overall diameter, 40 mm, and 45 mm respectively, than the severely damaged drive belts, A and B.
To maintain the pre-set factory tension settings during the occurrence flight, the clutch actuator is likely to have applied additional load to the rear 2 intact drive belts (C and D). The observed stretching of drive belts C and D may be an indicator that the helicopter had operated with just those 2 drive belts for an extended period during the occurrence flight, after A and B had dislodged from the fitted position and become damaged.
Figure 8: Damage to forward drive belt (Belt A)
Source: ATSB
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] The presence of the clutch light flickering indicates the clutch is moving to take up normal drive belt looseness in operation.
[2] Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.
[3] Dynamic rollover: The helicopter rolls or pivots around a skid, or landing gear wheel, until a critical rollover angle is reached. The main rotor thrust then continues the roll and the helicopter rolls onto its side, regardless of cyclic control correction inputs.
[4] A report for this incident was released by the ATSB as occurrence brief AB-2020-015.
[5] The overhaul of the complete helicopter is carried out each 2,200 hours or 12 years, time-in-service of the helicopter.
[6] An engineering order is an approved modification, repair or alteration to an aircraft or system.
[7] There was no published limit to the amount of time that the drive belts could remain in a stretched condition between starts
At about 1701 on 22 February 2021, a road-train truck drove into the path of a freight train at the Yarri Road level crossing in Parkeston, Western Australia. The train collided with the truck, resulting in the derailment of the train’s locomotive. The level crossing was fitted with active control devices encompassing railway crossing flashing signal assemblies, which were operational prior to the collision.
The locomotive and truck were substantially damaged in the collision, and the 2 drivers on board the train were seriously injured.
What the ATSB found
The ATSB found that the road-train truck driver engaged in tasks related to setting up the truck cabin while approaching the level crossing. This distracted their attention away from the road ahead and probably contributed to them not identifying the flashing lights (indicating the presence of a train) until it was too late to stop.
The level crossing design was consistent with the applicable Australian standard and provided sufficient opportunity for attentive drivers to identify the flashing light level crossing controls and stop. Due to the curved geometry of Yarri Road approaching the level crossing, drivers needed to look ahead and across the curve to see the crossing lights. Because of the effects of distraction, the truck driver was probably only looking at the section of road directly ahead of their vehicle and did not look at the crossing lights.
What has been done as a result
As a result of this accident, the road-train truck company (MLG Oz) implemented an awareness campaign and supporting processes prohibiting the presence of mobile phones and mobile phone cradles with the cabin of its vehicles. Additionally, in coordination with the rolling stock operator, Aurizon, MLG Oz has undertaken a joint exercise to understand the constraints both truck drivers and locomotive drivers face utilising level crossings on a daily basis.
The road owner, City of Kalgoorlie-Boulder has removed vegetation to improve sighting at the level crossing. Main Roads Western Australia are currently reviewing the speed zones along Yarri Road, with discussions held with the City of Kalgoorlie-Boulder to consider extending the 60 km/h zone to incorporate the level crossing. Additionally, a feasibility study is planned to determine if active advance warning assemblies can be installed on the approaches to the level crossing.
Associated with the number of recent collisions and their potential consequences, the ATSB has commenced a safety study into level crossing collisions involving trains and heavy road vehicles in Australia.
Safety message
This incident highlights, for truck drivers (and other road users), the importance of completing preparatory set up of their cab prior to moving their road vehicle, or stopping their vehicle to undertake and complete these tasks. Distraction can significantly impair driving safety. Even though it may be possible to occasionally glance at the road ahead while engaged in another task, critical information from the broader road environment may not be effectively perceived and comprehended, particularly on curved road approaches to level crossings.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 22 February 2021, train 2C74 departed Parkeston, Western Australia, for a shuttle service to West Kalgoorlie. The freight train, operated by Aurizon, consisted of one locomotive (Q4002) and 12 wagons. The crew comprised a driver and a tutor driver.
At about 1700,[1] 2C74 (travelling west) rounded a left curve, which led onto a 500 m straight section of track approaching the Yarri Road level crossing. At the same time, a road-train truck with 3 trailers, designated fleet number TK070 and operated by MLG Oz, was travelling north on Yarri Road (Figure 1).
The northbound road approach to the Yarri Road level crossing consisted of a sweeping right curve leading up to the crossing (Figure 1). Two passive level crossing advanced warning signs provided advice to approaching road traffic of a crossing ahead, one located at the beginning of the curve and the other about half distance through the curve. At about the location of the second sign were ‘Rail X’ road markings.
Figure 1: Aerial view of the level crossing approach and road alignment
The road-train truck was travelling north along a sweeping right curve on Yarri Road before approaching the railway crossing. The train was travelling west.
Source: Google Earth, annotated by ATSB
The active controls at the level crossing began operating (flashing) when the train was about 440 m away and travelling at about 35 km/h.[2] A few seconds later, the train driver sounded the locomotive horn.[3] At this time, the truck was about 800 m from the crossing and travelling about 50 km/h,[4] though gradually accelerating. The truck driver reported that, at about this time, a mobile phone cradle that they had previously fixed to the truck windscreen, via its suction cup, dropped off of the windscreen. The truck driver then set about cleaning and reattaching the mobile phone cradle, before inserting their mobile phone.
When the train was about 200 m from the crossing, the truck was just passing the first warning sign, about 350 m from the crossing. The train driver sounded the locomotive horn a second time when about 175 m from the crossing. About 6 seconds later and about 120 m from the crossing, the train driver sounded the horn a third time. At about the same time, the truck driver, still engaged with setting up their mobile phone in the cradle, was passing the second warning sign, about 160 m from the crossing. During this period, the train was travelling at about 37 km/h and the truck about 70 km/h, and neither driver had noticed the other vehicle approaching the crossing.
About 5 seconds after passing the second warning sign, the truck driver noticed the level crossing flashing lights and then, shortly after, the train approaching from the right. The truck driver reacted by applying the brakes, causing the trailer brakes to lock up and introduce wheel skid. At almost the same time, the train’s tutor driver, participating in a crossing check of the level crossing with the train driver, observed the truck approaching the crossing from their left and gave warning to the train driver. The train driver reacted by placing the locomotive brake handle in the emergency position. The train at this point was about 40 m from the crossing.
Neither vehicle could stop in time to avoid a collision. At about 1701, the truck drove into the path of the freight train, and the train collided with the truck’s first trailer. The force of collision resulted in the derailment of the locomotive, which came to a stop about 40 m after the crossing (Figure 2). Both train drivers were seriously injured and required hospital treatment.
Figure 2: Locomotive, post-collision
Image taken towards the east of the locomotive post-collision. Also visible are the rear 2 trailers of the road-train truck TK070.
Source: Aurizon, annotated by the ATSB
The truck’s prime mover uncoupled from its trailers, left the road and came to a stop about 50 m after the crossing. The truck’s first trailer came to rest between the prime mover and locomotive on the northern side of the track, and the truck’s second and third trailers stopped on the southern side of the level crossing. The truck driver was shaken but otherwise unhurt.
Context
Level crossing information
Kalgoorlie is a regional city located about 595 km east-north-east of Perth, Western Australia. Parkeston is a suburb of Kalgoorlie, located about 3 km north-east of Kalgoorlie city centre (Figure 3).
Figure 3: Location of Parkeston, Western Australia
Source: NatMap, Geoscience Australia, annotated by the ATSB
The rail line through Kalgoorlie is part of the interstate rail network between Adelaide and Perth and provides passenger and freight services. The Yarri Road level crossing is near the interface between the Australian Rail Track Corporation (ARTC) network to the east, and the Arc Infrastructure rail network to the west. The ARTC was the designated rail infrastructure manager for the level crossing, and the City of Kalgoorlie-Boulder was the road manager.
The level crossing comprised a single standard gauge track that intersected the roadway at an angle of about 35/145°.
Yarri Road is a sealed road carrying traffic between Kalgoorlie and locations to the north-east of the town, including some mine sites. The road runs in a north-south orientation before curving right immediately prior to the level crossing, for traffic approaching from the south. The speed limit was 80 km/h for the section of road approaching the level crossing from the south. The speed limit increased to 100 km/h a short distance to the north of the level crossing. Yarri Road was part of the approved route[5] for MLG Oz for its regular road-train operations.
The land adjacent to Yarri Road on the approach to the level crossing was sparsely vegetated with low-lying scrub and a few trees. There was a slight gradient, with the road being higher than the train line around the vicinity of the rail approach to the east of the level crossing, reducing to level as the train line approached the level crossing.
The Australian Level Crossing Assessment Model (ALCAM) is an assessment tool used to identify hazards and risks at level crossings, and to assist the prioritisation of level crossing upgrades. The most recent calculation of ALCAM ratings for the Yarri road crossing was conducted in October 2018. This assessment noted an average annual daily road usage of 200 vehicles per day and an average train volume of 20 trains per day, and it determined a medium high risk of collision at the crossing, with a predicted 125 years between collisions.
The level crossing featured active[6] traffic control devices (flashing light level crossing controls and bells) and passive[7] road surface markings and roadside signage for both road approaches. Further information about the traffic control devices is provided in Traffic control devices at Yarri Road level crossing.
Environmental conditions
Conditions on the day of the accident included clear weather, with a temperature of 31.4 °C recorded at 1500 at the Kalgoorlie-Boulder airport weather station. There had been no significant rainfall recorded for 2 days prior to the accident. Camera footage from the road-train truck showed that there were no environmental factors affecting visibility along the road ahead at the time of the accident (see also Figure 7).
At 1700, the sun was at an altitude of 19.61° from the horizon, with an azimuth of 269.75°. As the road-train approached the level crossing, the sun was to the truck driver’s left, moving further behind the driver as they rounded the curve. With the flashing light level crossing controls aligned to the road centreline at about 220°, sunlight would have shone on the lights from an angle of about 70°. Given the relatively obtuse angle of the sun on the level crossing, and because the warning assembly comprised light-emitting diode (LED) type lights with hooded housings including a black supplementary target board to enhance visibility, the position of the sun was unlikely to have affected the truck driver’s ability to see the flashing light level crossing controls.
Train and train crew
Train 2C74 was 249.7 m in length, with a total weight of 335.6 t. No evidence was identified to indicate there were problems with the train’s braking performance or other train systems that were potentially relevant to the accident.
The rail crew consisted of 2 drivers; a driver in the left driver’s seat and a tutor driver, who had just stood up out of the observer’s seat at the time of the collision. The driver was a qualified driver receiving practical route tuition for the West Kalgoorlie to Parkeston route on the day of the accident.
The train crew reported that, proceeding towards the level crossing, they conducted a crossing check, with each driver checking the road approach to their side of the train, and each calling ‘all clear’. A few seconds after hearing the ‘all clear’ from the driver, the tutor driver cross-checked for left-side traffic. They saw the approaching truck TK070 and identified it was not going to stop. Shortly after, the driver applied emergency braking. The ATSB determined that, at the point the train crew conducted the initial crossing check, it was unlikely they could have taken any action to prevent the collision.
The resulting forces of impact to the locomotive (Q4002) of train 2C74 did not compromise the survivable space available to the train crew. The train crew injuries were as a result of being thrown around within the locomotive cabin due to the rapid deacceleration triggered by the impact.
The actions of the train crew prior to the collision were consistent with Aurizon’s emergency response training. As such, the train handling, train speed and train driver actions were not considered factors in this collision.
Road-train truck driver
The road-train truck driver had been employed by MLG Oz since 2018 and held the appropriate driver’s licence for operating the type of vehicle used on the day of the accident. The truck driver said they were very familiar with the level crossing at Yarri Road and had never seen a train there before.
Prior to commencing duty at 1630 on the afternoon of the accident, the truck driver undertook an MLG Oz test for blood alcohol concentration at about 1617, with no alcohol detected. Following the accident, the Western Australia Police Force conducted tests for the presence of an illicit drug and alcohol, which provided a negative result (that is, no alcohol or drugs were detected).
The truck driver was rostered on day shifts from 14–18 February and on night shifts for 19–22 February. The night shifts commenced at 1630 and ended at 0500, with a 1-hour break. The driver reported that they were not feeling tired on the afternoon of the accident, having slept well for about 7 hours before starting work. Overall, there was insufficient evidence to conclude that fatigue or non-work-related factors were affecting the driver’s performance in the period leading up to the accident.
Road-train truck information
Road-train truck TK070 consisted of a Mack Titan Tri Drive prime mover and 3 side-tipping trailers in A-Triple configuration (Figure 4). The road-train was loaded with 97.5 t of ore and had a combined mass of about 148 t.
Figure 4: Tri-Drive road-train combination in A-Triple configuration
The image shows a Tri-Drive prime mover with trailer combination in A-Triple configuration.
Source: MLG Oz
Post-accident inspection by the Western Australia Police Force found that the overall braking performance of the prime mover and first trailer met the requirements prescribed by regulations.[8]
Road-train onboard monitoring system
The prime mover was equipped with an in-cab driver monitoring system, comprising a driver-facing camera as well as other sensors and hardware. This system was configured to provide in-cab and back-to-base alerts and data if it detected signs of driver fatigue or distraction. The prime mover was also equipped with forward-facing and side-facing cameras.
The driver started their journey about 3 minutes before the collision. Footage from the driver-facing camera showed the period leading up to the collision. From about 1 minute before the collision, the footage showed the driver engaged in several activities related to configuring the cab for the journey. This included using a spray bottle to clean the suction cup of a mobile phone cradle, manipulating the mobile phone cradle, and placing the mobile phone into the cradle in front of the driver. There was no evidence of any incoming or outgoing SMS[9] messages or voice calls during this period.
When interviewed by the ATSB after the accident, the driver identified that manipulating the mobile phone cradle and the phone probably distracted them. However, the driver also said that manipulating the phone cradle was a simple task that could be conducted in a couple of seconds. The driver thought this was about as long as it took to fix the cradle and they had completed interacting with the phone before rounding the curve on the approach to the level crossing. This recollection was not consistent with the in-cab video, which showed it took about 30 seconds from when the driver picked up the phone cradle to when they appeared to have their hands free from this task. The footage also showed that the driver’s eyes appeared to remain focussed on objects in the cab and on the dash after the truck entered the straight section prior to the level crossing.
When compared with footage from the forward-facing camera, the driver-facing footage showed that the driver’s eyesight appeared mainly focussed on activities within the cab throughout the approach to the level crossing. When the truck was at the position of the second warning sign (about 170 m prior to the level crossing), the forward-facing footage showed the train visible and slightly right of straight-ahead. The driver did not appear to look at or notice the flashing light level crossing controls or the train until about 5 seconds before the level crossing.
The ATSB obtained a report produced by the manufacturer of the in-cab monitoring technology, which stated that the monitoring system did not detect any ‘distraction events’ during the journey before the accident. The manufacturer advised that the system was configured to detect distraction by tracking head movements. Distraction events were identified when a driver’s head moved outside a specified range of movement for a specified length of time. In this instance, the driver did not need to make large head movements to manipulate the mobile phone cradle, and the glances away from the target field of view were less than the threshold time. Although it was evident the driver’s attention was directed in part towards cab configuration activities rather than focussed on the driving task, there was no suggestion the in-cab monitoring technology was deficient within its operational specifications.
Traffic control devices at Yarri Road level crossing
Background information
Given the size and weight of most trains, it is not possible for them to brake at anywhere near the rate of a road vehicle. In most circumstances, by the time a train driver can sight an approaching motor vehicle and decide whether it will stop, the train is already close to the railway crossing. In such circumstances a train driver is unable to take any effective action to avoid the collision other than sound the locomotive horn to warn the motorist, and (if time permits) make an emergency brake application.
By comparison, a road vehicle can stop relatively quickly. It is for this reason that, regardless of the type of crossing control (passive or active), the onus to take appropriate action to avoid a collision rests almost entirely with the road vehicle user.
The critical requirement at crossings with active controls is the road vehicle user’s ability to sight the flashing lights, recognise their intended message and react in accordance with the road rules. Consequently, it is important that active controls are effective at alerting the road user that they are approaching a railway crossing, with sufficient time for them to stop safely before entering the crossing.
There are 2 standards relevant to railway level crossings in Australia:
Australian Standard (AS) 7658:2020 Level crossings – rail industry requirements. AS 7658 was prepared by the Rail Industry Safety and Standards Board (RISSB) with input from various railway organisations. The standard specified minimum operational and engineering requirements for the life cycle of a level crossing. The requirements were intended to supplement details prescribed in AS 1742.7 (following).
Australian Standard (AS) 1742.7:2016 Manual of uniform traffic control devices Part 7: Railway crossings. AS 1742.7 specified the traffic control devices to be used to control and warn road traffic at and in advance of railway level crossings.
Flashing signals – minimum warning time
Both AS 7658 and AS 1742.7 stipulated that, where flashing light level crossing controls are installed, a minimum warning time of 20 seconds[10] be provided between the activation of the flashing lights and the arrival of the train. This was intended to allow road vehicles:
to stop before entering the crossing, or
if unable to stop, to traverse and clear the crossing before a train arrives.
The ATSB established that the flashing lights had been operating for about 45 seconds before the arrival of train 2C74 at the Yarri Road level crossing. Therefore, from a timing perspective, the crossing exceeded the timing requirements of both AS 7658 and AS 1742.7.
Level crossing configuration
AS 1742.7 illustrated the requirements for several crossing configurations, such as straight road approaches, sharp curves immediately prior to a crossing, and a crossing near road junctions. The standard did not specify any control treatment variations for sweeping road approaches such as existed at the Yarri Road level crossing. The only curved approach referenced was in relation to the orientation of signage and flashing lights. The standard advised that level crossing signage should be oriented towards the approaching traffic rather than the road edge, with flashing lights oriented to be visible from any point along the stopping sight distance[11] sight line.
Consequently, the ATSB examined the Yarri Road approach with respect to the straight road approach treatment specified in the standard. Figure 5 (left) shows the minimum treatment as specified in AS 1742.7. An examination of road markings and signage at the Yarri Road level crossing identified slight variations from the requirements specified in the standard. Figure 5 (right) shows the configuration installed at the Yarri Road level crossing on 22 February 2021.
Figure 5: Comparison of traffic control required by AS 1742.7 (left) with the controls installed at Yarri Road level crossing on 22 February 2021 (right)
Note that the illustration shows the road for a straight road approach, whereas the Yarri Road approach consisted of a sweeping right curve.
Source: AS 1742.7-2016 Figure 4.6, with right comparison image annotated by the ATSB
The points of note are:
The optional ‘Railway crossing width marker assembly’ (RX-9) had been installed at the Yarri Road level crossing (Figure 5, Note 1). The standard stated that this assembly should be used ‘…where the conspicuity of the crossing needs to be enhanced, typically on high-speed rural road approaches.’
The flashing signal assembly (RX-5) installed at the Yarri Road level crossing included a large black supplementary target board (Figure 5, Note 2). The standard suggested that a black supplementary target board of suitable size may be used to enhance the visibility of a flashing signal.
A ‘Railway crossing flashing signal ahead’ sign (W7-4) was positioned approximately 170 m before the flashing light assembly (Figure 5, Note 3). This was consistent with a level crossing approach design based on 85% of road vehicles travelling between 75–90 km/h (V85), noting the road speed limit was 80 km/h.
A second (optional) ‘Railway crossing flashing signal ahead’ sign (W7-4), with distance plate (W8-5), was positioned 350 m before the flashing light assembly (Figure 5, Note 4). This was positioned on the straight section of road before the curved approach.
Overall, the level crossing configuration was generally consistent with AS 1742.7.
Stopping sight distance
Main Roads Western Australia (MRWA) manages and regulates the movement of heavy vehicles over pre-approved routes in Western Australia, known as Restricted Access Vehicle (RAV) networks. Yarri Road was approved for RAVs up to AAB-Quad configuration. Although truck TK070 in A-Triple configuration had the same maximum vehicle length as the AAB-Quad configuration, the A-Triple configuration had a lower maximum combined vehicle mass.
AS 1742.7 provided guidance for calculating the stopping sight distance for various vehicles (AAB-Quad presenting the worst-case scenario). This guidance included the general case assumption of 2.5 seconds perception reaction time while travelling at the speed limit.
Using the guidance documented in AS 1742.7, the stopping sight distance for a road-train in AAB-Quad configuration, traveling at the road speed limit of 80 km/h, was calculated as 199 m. For RAVs travelling roads in Western Australia with speed limits above 60 km/h, MRWA applied additional speed limits of 10 km/h less than the posted speed limit. At a road speed of 70 km/h, the calculated stopping sight distance for an AAB-Quad would reduce to 165 m.
Sighting surveys conducted by MRWA prior to the accident recorded an observed sighting distance of 220 m[12] for northbound vehicles approaching Yarri Road level crossing. For a vehicle travelling at 80 km/h, this would provide about 9.9 seconds continuous sighting of the level crossing warning lights. At 70 km/h, this would extend to about 11.3 seconds, providing 2.8 seconds more than the minimum (2.5 seconds) perception reaction time.
In this case, the flashing lights at the Yarri Road level crossing were operating for about 45 seconds. Consequently, the lights were flashing for the entire time while truck TK070 was within sighting distance of the crossing. Similarly, the available sight distance exceeded the required stopping distance, so there was sufficient time for the driver to observe the flashing lights, react and stop before the level crossing.
Flashing light conspicuity
The ARTC advised that the flashing lights at the Yarri Road level crossing comprised 10 high intensity LED lamp units in a combination of main lights and back lights, focussed at each road approach. Examination of data recorded by the railway crossing event logger supported that all LED lamps were functioning at the time of the collision.
LED lamp units provide high intensity illumination over a wide viewing angle and provide good performance (warning), from a road user perspective, compared to traditional incandescent lamps. LED lights are also less susceptible to the effects of sun glare and reflection. According to the manufacturer’s specifications, the LED lamp units in use at Yarri Road had a range of about 700 m and a light beam spread of 30°.
AS 7658 specified that site-specific focussing diagrams should be prepared to optimise the visibility of flashing light installations at level crossings. The engineering plans for the Yarri Road level crossing specified that the warning lights for the direction that the road-train truck approached be focussed towards the centre of the road at about 120 m from the lights (near the ‘Rail X’ road markings). Given this focus and the beam spread of the lights, they would have been visible from a northbound vehicle for all of the 220 m sighting distance (Figure 6).
Figure 6: LED light beam spread and vegetation affecting sighting distance on northbound approach to Yarri Road level crossing
Image shows the LED light beam spread for the northbound approach to Yarri Road level crossing, as well as the vegetation on the eastern side of the road. Note that the light spread encompasses the entire area from when the warning lights come into view after passing vegetation on the eastern side of road.
Source: Google Earth and WA Police Service, annotated by the ATSB
Curved level crossing road approach
The southern (northbound) approach to Yarri Road level crossing consisted of a sweeping right curve, before straightening about 70 m prior to the crossing. For this approach configuration, a road vehicle driver’s line of sight would need to look through the curve, across vegetation on the inside of the curve, to be capable of sighting the flashing lights (Figure 7). It is not until the vehicle is much closer to the crossing that a driver’s vision along the road would also coincide with line of sight to the crossing. By this time, it would be unlikely that a large multi-trailer truck, travelling at the speed limit, would be able to stop before the level crossing. It is for this reason that a driver must continuously scan the road ahead, so action can be taken to avoid hazards. In this case, scanning includes looking through the curve, identifying the flashing lights and bringing the vehicle to a stop in a controlled manner.
Figure 7: Curved road approach to the level crossing
Note that the 2 images show the curved road approach from about 180 m from the level crossing. The top image shows the approach overhead with an indication of the road-train truck driver’s line of sight. The bottom image shows a screen capture from the forward-facing video camera on road-train truck TK070 with the driver’s sight lines to the road and the level crossing ahead.
Source: MLG Oz and Google Earth, annotated by the ATSB
Notifiable occurrences
A search of the Office of the National Rail Safety Regulator (ONRSR) notifiable occurrence[13] data was conducted for similar events at the Yarri Road level crossing. The search was limited to level crossing near misses and collisions from the date[14] that ONRSR commenced rail safety regulation in Western Australia until the date of this accident. The search returned only one related record, details of which included:
A near miss with a B-Double fuel tanker at 1213 on 24 July 2017. The report noted that the B-Double tanker was able to stop in a safe location after taking evasive action, with the train crew reporting that they did not have enough time to apply emergency brake. The report did not state the direction that the B-Double fuel tanker had approached the Yarri Road level crossing.
Safety analysis
Road-train truck TK070 proceeded through the level crossing at Yarri Road while the flashing light level crossing controls were activated, and into the path of freight train 2C74. The truck driver had not noticed the flashing lights, and only noticed train 2C74 at a time when it was too late to prevent the collision. When the train crew of 2C74 saw the truck and identified that it was not going to stop for the crossing, it was too late for them to stop their train or reduce the severity of the impact.
This accident demonstrates that the safety of road and rail traffic at level crossings is dependent on road users attending to and responding to the level crossing controls. This is particularly the case for heavy vehicle road traffic, whose greater mass poses a greater hazard to rail traffic in the event of a collision.
The level crossing configuration was generally consistent with AS 1742.7. The flashing light level crossing controls were activated for the entire time truck TK070 was within sighting distance of the crossing. Although there was a sweeping curve on approach to the crossing, there was sufficient sighting for a driver scanning for hazards along the road ahead to react and stop before the level crossing. Overall, the ATSB concluded that the operation, design and maintenance of the level crossing was unlikely to have been contributory to the development of this accident.
Distraction occurs when a driver’s attention (meaning where the driver is looking, what they are manipulating/touching, and what they are thinking about) is diverted from activities critical for safe driving towards a competing activity (Parnell and others 2016). Research has shown that distracted drivers:
spend more time looking at objects in front of their vehicle and less on objects in the periphery
make fewer ‘anticipatory glances’ towards potential hazards
notice fewer objects in the driving scene, being more vulnerable to ‘look but failed to see’ errors (Strayer and Fisher 2016).
The effects of distraction can be insidious, since drivers can often be unaware of the extent to which their performance has been impaired. Performance can be impaired for up to 20 seconds after attention is redirected back to the primary driving task following a distraction (Bowden and others 2019). As such, even when a driver presumably believes that they are no longer distracted due to re-focussing on the road ahead, their performance may still be impaired.
Mobile phones can be a significant source of distraction for road vehicle drivers. Drivers who use their mobile phones while driving take longer to respond to hazards and other objects, have reduced sampling of information such as mirrors and speedometers, and are less able to maintain the position of their vehicle on the road (Caird and others 2014; Caird and others 2018). This is partly because of the interference caused by looking at and manipulating a phone or other technology, and partly because of the cognitive distraction caused by thinking about activities like holding a conversation (Young and others 2003). Research has also demonstrated that driving performance is similarly impaired by other in-vehicle technology such as navigation and entertainment systems (Ranney and others 2011).
Shortly after commencing the journey along Yarri Road, the road-train truck driver engaged in activities primarily related to configuring the cab, including setting up a dash-mounted mobile phone cradle and placing a mobile phone in the cradle. Although the driver was not using their mobile phone to dial or text, the interaction with the phone distracted the driver from the task of driving the truck, causing them to divide their attention between driving and manipulating the phone and its cradle, and to look away from the road ahead. The driver’s visual attention was diverted from the road ahead for significant periods during the 1 minute prior to approaching the level crossing, including during the critical period of the approach to the level crossing where the flashing light level crossing controls were visible and there was sufficient distance to stop.
The truck driver had never seen a train on previous journeys across the Yarri Road level crossing, and it is possible that a low expectancy of encountering a train contributed to the truck driver allocating a low level of attention to the crossing. Studies have found that drivers who are familiar with a level crossing are more likely to be involved in a crossing incident than drivers unfamiliar with the crossing, partly because they do not expect to encounter a train (Yeh and Multzer, 2015).
Due to the curved geometry of the road approaching the level crossing, the flashing light level crossing controls were located away from the driver’s straight-ahead line of sight. This continued until the truck approached the crossing straight-on, about 70 m before the crossing. Consequently, the driver needed to look through the curve of the road to see the flashing warning lights at the crossing in time to stop for the train. Due to distraction, the driver only made occasional glances ahead of the truck, probably only attending to objects immediately in front, and ensuring the truck remained on the road. The driver was probably not effectively scanning further ahead of the truck and through the curve to the crossing lights.
The driver of the road train thought they could safely re-attach the mobile phone cradle and conduct other activities while still operating their vehicle, believing this would only take a short time and take a small amount of effort.[15] This accident shows that even the simplest of tasks can distract attention away from the road ahead, sometimes at critical times when attention is required to detect signals, hazards or other road users. Wherever possible, it is safest to perform secondary tasks before commencing the journey or after pulling over and stopping the vehicle.
A small proportion of level crossing collisions tragically result in fatalities and/or serious injuries to those on board road vehicles. In addition, some level crossing collisions that involve heavy road vehicles can result in serious adverse consequences to those on board trains. The ATSB also noted that there were 11 collisions between heavy road vehicles and trains at level crossings in Australia between July 2020 and June 2021 (and 23 such collisions over the previous 5 years).
Accordingly, in 2021, the ATSB commenced a safety study into level crossing collisions involving trains and heavy road vehicles in Australia.[16] The study includes a review of previous collisions to determine their characteristics and circumstances, and also determine if there are any unidentified systemic safety issues or learning opportunities that could enhance the safety of future transport operations.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision between a road-train truck and a freight train at the Yarri Road level crossing near Parkeston, Western Australia, on 22 February 2021.
Contributing factors
While approaching the level crossing, the road-train truck driver engaged in several tasks related to setting up the truck cabin, taking attention away from the road ahead. As a result, the driver was distracted during the critical period when it was possible to notice the flashing light level crossing controls in time to stop for the train.
Other findings
The Yarri Road level crossing configuration provided sufficient sighting and stopping distance for an attentive road vehicle driver to notice the flashing light level crossing controls and bring the vehicle to a controlled stop before the level crossing.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Safety action by Aurizon
Aurizon advised it had completed the following proactive safety actions:
Aurizon engaged with Main Roads WA, ARTC, and ARC Infrastructure to understand the current Yarri Road ALCAM assessment, existing controls and potential for additional controls (such as active advanced warning assemblies). Main Roads WA has confirmed to Aurizon that the ALCAM assessment had been reviewed and updated. Main Roads WA advised Aurizon that it does not believe any changes to the level crossing are required based on a review of the accident. Aurizon will continue to work with Main Roads WA on strategies to reduce driver distraction.
Aurizon engaged with the road manager for Yarri Road, the City of Kalgoorlie-Boulder, to ensure there is a commitment to maintaining vegetation to a suitable level to ensure clear sighting distances at Yarri Road level crossing are maintained.
Aurizon has conducted a learning team with MLG Oz and QUBE to understand the constraints both truck drivers and locomotive drivers face utilising level crossings on a daily basis. A number of occurrences were also discussed, including this accident.
Aurizon conducted an emergency management risk review in September 2021.
Aurizon scripted and developed an awareness video, which will be distributed to staff as part of a level crossing reporting awareness program that is under development.
Aurizon stated it was also continuing to progress with the following proactive safety actions:
Occurrence and engineering data is being analysed to determine a location of safety in the locomotive cab (including raising discussions regarding seat belts/air bags for locomotives with the Rail Industry Safety and Standards Board as an industry-wide issue).
A locomotive familiarisation session is being conducted with the Department of Fire and Emergency Services (planned for April 2022).
Engineering data associated with crash pulse and energy management is being reviewed, using data gained from this accident. This review is being conducted in 2 phases:
short-term – a high-level analysis to provide clear options to drivers about positions of safety in the locomotive.
long-term – in conjunction with relevant industry working groups, complete detailed analysis on crash pulse and energy management in locomotives to define a position of safety and any design needs for locomotives.
A potential automated emergency warning notification device has been identified and is expected to be trialled in early 2022.
Options are being investigated to install an emergency tap (emergency brake) for the second driver to activate while seated in a Q class locomotive.
In addition, Aurizon advised that it continues to work with rail infrastructure managers and road managers on targeted intervention at high-risk level crossings. A working group is being stood-up to provide additional coordination to activities across multiple interfaces.
Safety action by Australian Rail Track Corporation
The Australian Rail Track Corporation made contact with the road manager for Yarri Road (City of Kalgoorlie-Boulder) and suggested that it consider the benefits of installing active advance warning assemblies.
Safety action by MLG Oz
MLG Oz advised that it had completed the following proactive safety actions:
reviewed its documentation and training that related to the use of mobile phones
delivered a use of mobile phones re-awareness campaign throughout the business, which was supported by the in-cabin footage from this accident
prohibited the use of mobile phone cradles within the cabin and reinforced that mobile phones were to remain out of reach in the driver’s crib/shift bag
added MLG Oz safety team to the in-cab monitoring system so that they will be notified of and could view distraction events, which will be reported on following monthly site visits
reviewed and updated the MLG Oz Trafficable Route risk assessment
produced an awareness video from the in-cabin footage obtained from this accident was used to outline how quickly a distraction event can result in a serious incident
reviewed MLG Oz’s Commercial Drivers Fatigue Management Plan and conducted a self-audit to ensure compliance with the Act
took part in a learning day with Aurizon to understand the constraints both truck drivers and locomotive drivers face utilising level crossings.
Safety action by City of Kalgoorlie-Boulder
The City of Kalgoorlie-Boulder advised that it had completed vegetation removal on the eastern side of Yarri Road to improve sighting towards the flashing light level crossing controls from the southern approach to the level crossing.
Safety action by Main Roads Western Australia
Main Roads Western Australia advised that it was currently reviewing the speed zones along Yarri Road. As part of this review, temporary traffic counters were being deployed along Yarri Road; these traffic counters will be used to determine the vehicle volumes, vehicle types and vehicle speeds along the road.
Discussions have been held with the City of Kalgoorlie-Boulder to consider extending the 60 km/h zone such that it incorporates the level crossing. A feasibility study is also being undertaken to determine if active advance warning assemblies can be installed on the approaches to the level crossing.
Sources and submissions
Sources of information
The sources of information during the investigation included:
the drivers of train 2C74
the driver of road train truck TK070
Aurizon
MLG Oz
Main Roads Western Australia
Western Australia Police Force
Australian Rail Track Corporation (ARTC)
Arc Infrastructure
City of Kalgoorlie-Boulder
Nine News
Telstra.
References
ARTC Annotated Code of Practice for the Defined Interstate Rail Network, Issue 3.0 - Volume 3, Operations and Safeworking Part1: Rules.
Baldauf D, Burgard E and Wittmann M (2009) ‘Time perception as a workload measure in simulated car driving’, Applied Ergonomics, 40:929–935.
Bowden VK, Loft S, Wilson MD, Howard J and Visser TA (2019) ‘The long road home from distraction: Investigating the time-course of distraction recovery in driving’, Accident Analysis & Prevention, 124:23–32.
Caird JK, Johnston KA, Willness CR, Asbridge M and Steel P (2014) ‘A meta-analysis of the effects of texting on driving’, Accident Analysis & Prevention, 71:311–318.
Caird JK, Simmons SM, Wiley K, Johnston KA and Horrey WJ (2018) ‘Does talking on a cell phone, with a passenger, or dialing affect driving performance? An updated systematic review and meta-analysis of experimental studies’, Human Factors, 60:101–33.
Parnell KJ, Stanton NA and Plant K (2016) ‘Exploring the mechanisms of distraction from in-vehicle technology: The development of the PARRC model’, Safety Science, 87:25–37.
Ranney TA, Baldwin GH, Parmer E, Martin J and Mazzae EN (2011) Distraction effects of manual number and text entry while driving, Report No. DOT HS 811 510, National Highway Traffic Safety Administration: Washington DC.
Strayer DL and Fisher DL (2016) ‘SPIDER: A framework for understanding driver distraction’, Human Factors, 58:5–12.
Yeh M and Multzer J (2008) Driver behaviour at highway-railroad grade crossings: A literature review from 1990–2006, Report No. DOT/FRA/ORD-08/03, Federal Railroad Administration: Washington DC.
Young K, Regan M and Hammer M (2003) Driver distraction: A review of the literature, Report No. 206, Monash University Accident Research Centre.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the drivers of train 2C74
the driver of road-train truck TK070
Aurizon
MLG Oz
Main Roads Western Australia
City of Kalgoorlie-Boulder
Australian Rail Track Corporation (ARTC)
The Office of the National Rail Safety Regulator (ONRSR).
Submissions were received from:
the drivers of train 2C74
Aurizon
MLG Oz
Main Roads Western Australia
ARTC
ONRSR.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 25 February 2021, a Piper Aircraft PA-28, registered VH-FPS, operated by Moorabbin Aviation Services, departed Warrnambool Airport for Moorabbin Airport, Victoria. The flight crew were conducting a training flight under the visual flight rules (VFR). There was an instructor, student pilot and a passenger on board.
During the cruise, the weather deteriorated and the aircraft was returned to Warrnambool. As the aircraft approached Warrnambool, the visibility reduced and the instructor initiated a climb into cloud. They contacted air traffic control and received navigation assistance to an area free from cloud. The flight then proceeded to Moorabbin Airport where the aircraft landed safely.
What the ATSB found
The ATSB found that although the flight crew had conducted a pre-flight briefing, they did not detect the forecast deteriorating weather in the Warrnambool area. In addition, they did not assess the aerodrome forecast for both Moorabbin and Warrnambool to ensure they were suitable destination airports. The aircraft departed Warrnambool in visual flight conditions however, as forecast, the weather subsequently deteriorated and the flight crew initiated a return to Warrnambool. During the return, the conditions reduced below that required for visual flight resulting in the VFR certified aircraft entering instrument meteorological conditions (IMC).
After entering IMC, the pilot requested assistance from the controller and maintained control of the aircraft.
What has been done as a result
As a result of this occurrence, the operator advised that they have developed a:
weather information board, which displays the synoptic charts, relevant TAFs and grid point wind and temperature charts for the day at the Moorabbin base.
Warrnambool PowerPoint presentation for dual and solo flight exercises, to emphasis the prevailing weather in that region of Victoria and Bass Strait.
supervision policy in the Training Management Manual to facilitate varying supervision based on the experience level and proven competency of the junior instructors and other circumstances which may challenge the junior instructor’s skill set.
company policy to provide organisational support for flight crew required to stay away from base overnight due to adverse weather, aircraft unserviceability or pilot incapacity/fatigue, including arrangement and payment of transport and accommodation if required. This policy will be promoted through both staff and student levels.
program on effective decision making to be delivered to all staff.
Safety message
Weather related incidents continue to be a significant concern in aviation safety. As stated in the ATSB publication Accidents involving Visual Flight Rules pilots in Instrument Meteorological Conditions,1 in 10 VFR into IMC events result in a fatal outcome. This report highlights that ‘thorough pre-flight preparation is the best defence against flying into deteriorating weather’.
The ATSB encourages pilots, of all experience levels, to develop the knowledge and skills required to avoid unintentional operations in IMC. However, if a VFR‑rated pilot does find themselves in marginal weather, they should seek whatever assistance is available, including contacting air traffic services.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On the morning of 25 February 2021 the flight crew of a Piper Aircraft PA-28-161 aircraft, registered VH-FPS (FPS) and operated by Moorabbin Aviation Services, arrived at Moorabbin Airport to prepare for a VFR training flight.[1] The flight crew consisted of an instructor and student pilot (student), with a second student pilot observing the flight. The flight was part of the navigation training for the student’s integrated commercial pilot licence training course.
The student obtained the weather forecast and completed the planning for the training flight, which was to depart Moorabbin Airport and overfly Bacchus Marsh, Ballarat, Ararat, Horsham, and then to Warrnambool, where they [2] planned to land before 1400. At Warrnambool, they planned to refuel, before returning to Moorabbin Airport (Figure 1).
Once the planning was complete, the student briefed the instructor on the forecast weather and the procedures for the flight. They identified that at the time of their arrival at Warrnambool, the aerodrome forecast (TAF) was forecasting the visibility to be greater than 10 km with scattered[3] cloud at 3,000 ft above ground level (AGL). However, at 1500 a forecast INTER[4] was due to commence, with the visibility decreasing to 5,000 m in showers of rain and the cloud cover increasing to broken[5] and the cloud base lowering to 1,000 ft AGL. The student pilot did not brief the instructor on deteriorating weather in the Warrnambool area which was forecast on the graphical area forecast (see the section titled Weather forecasts) and the instructor did not detect this omission. The instructor later advised that they did not put enough emphasis on considering the weather forecast during this briefing.
Figure 1: Flight planned track and diversion
The red full line shows the flight track, which was planned and flown, the red broken line shows the intended flight planned track and the blue line shows the track flown after the diversion from Lake Goldsmith, near Ballarat, to Warrnambool.
Source: Google earth, annotated by the ATSB
The flight departed Moorabbin Airport at around 1200 Eastern Daylight-saving Time,[6] an hour later than planned, with the student flying the aircraft from the left seat. After passing Ballarat at 4,500 ft above mean sea level (AMSL), the instructor put the student under the hood,[7] to practise flying with reference to instruments only. After flying for about 14 minutes, the hood was removed and the instructor asked the student to identify the location of the aircraft. The student correctly identified the aircraft’s position and the instructor then tasked them to divert directly to Warrnambool, which they did successfully.
The instructor advised that the aircraft landed at Warrnambool at around 1400. The weather was clear however, as they parked the aircraft, the wind strength increased. As an air ambulance helicopter was due to land and refuel, the student and passenger took a short break in the terminal. While the helicopter was refuelling, the cloud cover increased and it began to rain. The flight crew waited until the rain stopped before commencing refuelling their aircraft.
The instructor advised that while waiting for the weather to improve, they checked the weather from various sources using their mobile phone. They observed that the TAF for Warrnambool had been amended and was now forecasting a TEMPO[8] with the visibility reducing to 4,000 m in showers of rain and the cloud had increased to broken with the base at 800 ft AGL. They could not recall how much of the graphical area forecast (GAF)[9] was reviewed and whether they checked the TAF for Moorabbin Airport at this time.
The instructor then contacted two senior pilots at their Moorabbin base and advised them that they were delayed at Warrnambool as the weather had deteriorated. Both of these pilots advised the instructor to wait until the weather had cleared and the senior base pilot advised them to remain at Warrnambool overnight if required.
The instructor reported that the cloud level subsequently lifted and the aerodrome weather information service (see the section titled Warrnambool airport observations) stated that the cloud was scattered at 1,900 ft AGL. A decision was made to depart, with the plan that they would return to Warrnambool if the weather deteriorated. The instructor advised that at the time of departure, while there were some clouds, there were also patches of blue sky and the visibility to the east was clear. However, they noted that there was an increased amount of cloud to the north-west of the airport.
It was reported that, during the initial cruise, the visibility was good but the cloud base lowered as the flight progressed. The student stated that during the cruise they were maintaining about 1,200 ft above mean sea level (AMSL) with the cloud base lowering to 1,300 ft. The instructor advised they were continually checking behind them to ensure they had clear weather to return to Warrnambool if required.
Due to the deteriorating weather, the instructor decided to divert to Cobden Airport to land and wait until the weather cleared. As the aircraft approached Lake Elingamite, about 5 km south-west of Cobden (see Figure 1), the visibility reduced significantly in rain. As a result, the instructor, in the right seat, took control of the aircraft. They stated they could no longer see Cobden Airport and a decision was made to return to Warrnambool.
Figure 2: Photograph taken en route to Cobden Airport
Source: supplied
The flight crew reported that during the initial stages of the return, the visibility was good. As they got closer to Warrnambool however, the visibility reduced, and they had to descend as the cloud base again began to lower. The instructor advised they were continuously listening to the AWIS during the return. At about 1615, while approaching Warrnambool township, at approximately 450 ft AGL, the instructor slowed the aircraft and extended two stages of flap. The visibility reduced significantly and the instructor, not wanting to descend further, made the decision to climb into cloud.
Figure 3: Photograph taken at 1613 during the return to Warrnambool Airport
Source: supplied
The instructor advised that they unsuccessfully attempted to contact air traffic control (ATC) to report that they were a VFR aircraft changing category to instrument flight rules (IFR).[10] They reported that they were having radio difficulties and this call may not have been received. Despite that, ATC responded to a call where the instructor advised they were in cloud and were requesting assistance. After clarifying the aircraft’s location and the pilot’s intentions, ATC assisted with information on the local weather, the lowest safe altitude and subsequently provided advice to keep the wings level, maintain a constant speed and to trust their instruments.
Initially the instructor maintained a shallow climb and a low angle of bank turn to remain within an area around Warrnambool known to be clear of obstacles. When they reached 3,000 ft, they turned north to ensure they did not track over water. They advised that in an attempt to fix the apparent radio problems they also switched between the two radio units in the aircraft and exchanged headsets with the student pilot. They continued the climb to 4,500 ft.
ATC identified the aircraft on radar and issued the flight crew with a heading to Avalon Airport as the pilot of a helicopter in that area had reported operating clear of cloud. During the cruise, the instructor became concerned that they would enter controlled airspace and requested a clearance at 4,500 ft, which was approved.
The aircraft exited cloud about 10 NM south-west of Avalon Airport, where the instructor requested, and was cleared for, descent to 2,500 ft. The flight then continued to Moorabbin Airport for an uneventful landing.
Context
Personnel information
Instructor
The grade three instructor held a valid Commercial Pilot Licence (Aeroplane), with a class 2 aviation medical certificate. They held an instrument rating with multi-engine aeroplane (IR-MEA), IAP 2D and IAP 3D endorsements.[11] They had completed an instrument proficiency check in March 2020 but had not conducted any instrument flying since that date.[12] In addition, they had never conducted instrument flying from the right seat of the aircraft.
They had accrued a total of 1,241 flying hours, having flown approximately 62 hours in the previous 90 days.
At the time of the incident, the pilot had a self-assessed fatigue level[13] of ‘2: very lively. Responsive, but not at peak’.
Student pilot
The student pilot held a recreational pilot licence and was training for their commercial pilot licence. They had accumulated approximately 81 hours of flying with approximately 17 hours in the previous 90 days.
Aircraft
The Piper PA-28-161 is a single engine, low wing, four seat aircraft. FPS was certified for day and night VFR operations only. The main aircraft flight instruments are located on the left side of the cockpit (Figure 4).
Figure 4: PA-28 cockpit
Source: supplied
Weather forecasts
The student received the graphical area forecast (GAF)[14] at 0910. It was valid until 1600. The GAF was split into six different areas on the day (Figure 5). The flight was planned to traverse two of these areas: B and C.
Area C
The initial section of the flight from Moorabbin Airport was planned in area C. This area was forecast to have greater than 10 km visibility and scattered cloud between 1,600 and 3,000 ft AMSL. From 1500, cloud was forecast to increase to broken between 3,000 and 8,000 ft AMSL.
Area B
The flight was then planned to enter area B, which included Warrnambool. From 1400, the visibility in this area was forecast to reduce to 3,000 m in scattered rain with broken stratus[15] cloud between 500 and 2,000 ft AMSL and broken stratocumulus[16] clouds between 2,000 and 9,000 ft AMSL.
Grid Point Wind and Temperature forecast
The Grid Point Wind and Temperature forecast valid at the time of the flight, forecast the wind to be at 27 kt from 249˚ in the Ballarat area and 11 kt from 249˚ in the Warrnambool area.
No AIRMETs[17] or SIGMETs[18] were issued during the validity period.
Figure 5: Graphical area forecast valid for flight
Source: Bureau of Meteorology, annotated by the ATSB
Warrnambool aerodrome forecast
The TAF for Warrnambool was issued at 0445 and was valid when the student received the information at 0938. It was forecasting visibility greater than 10 km and scattered cloud with a base at 3,000 ft AGL. An INTER was forecast from 1500, where the visibility was forecast to reduce to 5,000 m in showers of rain with broken cloud at 1,000 and 2,500 ft AGL.
The Bureau of Meteorology released an amended TAF at 1243, after the aircraft had departed Moorabbin Airport. It forecast that at the time of their arrival the visibility would be greater than 10 km, with showers of rain and few[19] cloud with a base of 1,500 ft AGL. The forecast INTER was due to commence at 1600 with visibility reducing to 5,000 m in showers of rain and a broken cloud base at 1,000 ft AGL. The crew did not receive this forecast.
At 1500, a second amended TAF was released that forecast visibility to remain greater than 10 km with showers of rain and scattered cloud with bases at both 1,000 and 2,000 ft plus broken cloud at 3,000 ft AGL. There was also a TEMPO associated with this TAF which commenced at 1500, forecasting the visibility to reduce to 4,000 m in showers of rain and broken cloud at 800 and 2,000 ft AGL.
Warrnambool airport observations
An automatic weather station (AWS) recorded actual weather conditions at Warrnambool Airport. The cloud base and amount is measured by a ceilometer, which is a device that uses a laser, or other light source, to determine the height of the cloud base. As such, it measures the cloud in one direction only and this may not give an accurate interpretation of the surrounding conditions.
The AWS recorded a SPECI[20] report about 5 minutes before the aircraft departed Warrnambool that showed the visibility was greater than 10 km with scattered cloud at 1,100 ft and broken cloud at 1,900 ft AGL.
While the aircraft was returning to Warrnambool, the AWS recorded that the visibility was fluctuating between 5,000–9,000 m, with cloud at 900 ft AGL, varying between broken and scattered.
Moorabbin Airport forecast
The TAF current at the time of departure from Moorabbin Airport, issued at 0505, was valid for the entire flight. It forecast CAVOK conditions at the time of departure and for the return to Moorabbin.[21] However, a new TAF was issued at 1032, before the flight departed Moorabbin, which was valid from 1100 to 2300. It also forecast conditions to be CAVOK during the flight, with deteriorating conditions associated with an INTER due to commence at 1900.
Flight planning
Civil Aviation Regulations (CAR), 239Planning of flight by pilot in command, stated that ‘before beginning a flight, the pilot in command shall study all available information appropriate to the intended operation, and in the cases of flights away from the vicinity of an aerodrome…current weather reports and forecasts for the route to be followed and at the aerodromes to be used’.
Aeronautical Information Publication (AIP) Enroute 1.10 Flight planning stated that the forecast information must include an airport forecast for the destination and, when required, the alternate airport. It also stated that if the pre-flight information is obtained more than 1 hour prior to the estimated departure time, updated information is required.
In addition, AIP Enroute 1.1 10.7.2 Weather conditions stated that when planning a day VFR flight in a fixed wing aircraft, an alternate airport is required when conditions at the destination airport are forecast to be cloud greater than scattered below 1,500 ft or visibility less than 8 km. If a TEMPO is associated with the forecast, which reduces conditions below this requirement, then the pilot is required to plan an alternate airport or to have enough fuel to hold for 1 hour.
Visual flight rules
Civil Aviation Regulations 1988 (CAR), 172Flight visibility and distance from cloud, outlined that flight under the VFR can only be conducted in visual meteorological conditions (VMC).[22] Additionally, when operating at or below 2,000 ft above the ground or water, the pilot must be able to navigate by visual reference to the ground or water.
In addition to minimum visibility and distance from cloud, a pilot is also required to maintain a minimum height above the ground. CAR 157Low flying, directs that a pilot in command must not fly the aircraft over:
any city, town, or populous area at a height lower than 1,000 ft; or
any other area at a height lower than 500 ft.
This does not apply if ‘through stress of weather or any other unavoidable cause it is essential that a lower height be maintained’.
Similar occurrences
Between 2011 and 2021, the ATSB was notified of 106 occurrences, where a VFR flight entered IMC. Of these, there were 13 accidents that resulted in 26 fatal injuries.
Safety analysis
Both the instructor and the student pilot advised that they assessed the weather forecasts during the pre-flight planning. They also both advised that they planned to land at Warrnambool before 1400, which was before the deteriorating weather was forecast to commence on the Warrnambool TAF. However, they did not assess the forecast deteriorating weather in area B on the GAF, which was also due to commence at 1400.
Additionally, as the flight left more than 60 minutes after the pre-flight weather forecasts were obtained, updated weather forecasts were required. However, the weather information had not changed significantly. The delayed departure and the time spent on the ground in Warrnambool both added to the likelihood of the aircraft encountering the forecast deteriorating weather.
The instructor advised that they checked the weather for the return flight while they were on the ground at Warrnambool. However, they used the TAF for Warrnambool and the surrounding airports, rather than the area forecast and Moorabbin TAF, to provide an indication of the likely weather to be encountered on return to Moorabbin. This was a missed opportunity to identify the forecast reduced visibility and low-level cloud subsequently encountered during the flight.
In addition, as the instructor planned to return to Warrnambool Airport if conditions deteriorated, they should have considered the forecast in relation to its use as a destination. As the TAF forecast a TEMPO with conditions deteriorating below the alternate minima requirements, they were required to plan for an alternate airport or have enough fuel to hold for 1 hour.
The flight crew had refuelled at Warrnambool, so the aircraft had sufficient endurance for the required holding. However, when planning to hold for 1-hour, consideration should also be given to the likely weather conditions – in this case, the conditions were forecast to have visibility reducing to 4,000 m and broken cloud at 800 ft AGL. The flight crew had experienced the rapidly changing weather environment, and consideration should have been given to how they were going to hold for 1‑hour in potentially poor weather conditions.
The instructor also did not adequately reassess the conditions at Moorabbin prior to departure from Warrnambool, however the conditions were suitable for the return flight.
Although the conditions on departure from Warrnambool were suitable for VFR flight, they soon deteriorated resulting in the decision to return. During the return to Warrnambool, the aircraft encountered forecast conditions which were no longer suitable for VFR flight and the instructor climbed the aircraft and entered cloud. The instructor had an instrument rating however, they had not practiced this skill in eleven months. In addition, the aircraft was not certified for instrument flight.
After making the decision to enter cloud, the instructor was conscious that they were not current and had never flown with reference to instruments from the right seat, which required them to use the instruments on an angle across the cockpit. Consequently, they ensured that they minimised control movements to maintain control of the aircraft. They also contacted ATC at the earliest opportunity to advise of their situation and request assistance. This ensured the instructor could concentrate on flying and maintaining control of the aircraft and also expedite the return to visual flight conditions.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the VFR flight into IMC involving Piper Aircraft PA-28, VH-FPS, near Warrnambool, Victoria on the 25 February 2021.
Contributing factors
While conducting preparation for the flight, neither the instructor nor the student pilot identified the forecast deteriorating weather in the Warrnambool area.
Prior to departure from Warrnambool, the instructor did not analyse either the Warrnambool or Moorabbin aerodrome forecasts for their suitability as destination airports. This probably resulted in them selecting Warrnambool as an alternate airport, despite the forecast temporary deterioration, and encountering poor weather conditions during the return to Warrnambool.
Conditions reduced below that required for visual flight resulting in the VFR‑certified aircraft entering instrument meteorological conditions.
Other findings
After entering instrument meteorological conditions (IMC), the instructor maintained control of the aircraft and requested assistance from air traffic control.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future.
Safety action by Moorabbin Aviation Services
As a result of this occurrence, the operator have developed a:
weather information board which displays synoptic charts, relevant TAFs and grid point wind and temperature (GPWT) chart for the day at the Moorabbin base
Warrnambool PowerPoint presentation for dual and subsequent solo exercises to emphasis weather in that region of Victoria and Bass Strait
supervision policy in the Training Management Manual to facilitate varying supervision based on the experience level and proven competency of the junior instructors and other circumstances which may challenge the junior instructor’s skill set
company policy to provide organisational support for flight crew required to stay away overnight due to adverse weather, aircraft unserviceability or pilot incapacity/fatigue, including arrangement and payment of transport and accommodation if required. This policy will be promoted through both staff and student levels
program on effective decision making to be delivered to all staff.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
flight crew
Moorabbin Aviation Services
Bureau of Meteorology
Airservices Australia
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
flight crew
Moorabbin Aviation Services
Bureau of Meteorology
Civil Aviation Safety Authority
Airservices Australia
Submissions were received from:
the instructor
Moorabbin Aviation Services
Civil Aviation Safety Authority
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.