In-flight break-up involving Robinson R22 Beta II, VH-RAS, 13 km south-west of Koorda, Western Australia, on 2 October 2022

Final report

Report release date: 21/05/2024

Executive summary

What happened

On the morning of 2 October 2022, a Robinson Helicopter Company R22 Beta II, registered VH‑RAS, departed Koorda, Western Australia for a private flight, with the pilot and one passenger on board. About 6 minutes later, the helicopter impacted terrain, inverted, about 13 km to the southwest of the departure point. The helicopter was destroyed, and both occupants were fatally injured.

What the ATSB found

Recorded flight data showed that, during cruise, the helicopter’s altitude increased by about 100 ft and then rapidly descended, almost vertically, before colliding with terrain inverted. The ATSB found that the helicopter sustained an in-flight break-up at about the time it rapidly descended. The site and wreckage examination identified signatures indicative of a low-g and/or low rotor RPM/rotor stall condition, however, the circumstances preceding this could not be determined.

Dual flight controls were fitted in a position that was occupied by the passenger. When carrying passengers, the helicopter manufacturer recommends removing the passenger‑side controls to avoid inadvertent bumping or interference.

The ATSB also found that the pilot had not disclosed their use of a prescription medication or the associated medical condition to the Civil Aviation Safety Authority. This precluded a specialist assessment of the aeromedical significance of the medication’s use and the underlying conditions for which it was prescribed.  

Safety message

Low-g and low rotor RPM/rotor stall conditions can be catastrophic for helicopters with semi‑rigid rotor heads. A pilot’s ability to identify the condition and promptly apply the correct flight control inputs is vital to effective recovery and continued safe operation. It is also particularly important that the dual flight controls be removed before flight to avoid inadvertent passenger interference. Where the dual controls cannot be removed, the passenger should be fully briefed to keep their hands and feet clear. 

This accident also highlights the importance of pilots reporting relevant medical conditions and the use of medications to their designated aviation medical examiner. A full understanding by the Civil Aviation Safety Authority’s aviation medical specialists of a pilot’s medical conditions, and use of medications, enables management of the risk for both the individual and flight safety overall.

Further, recording devices have long been recognised as an invaluable tool for investigators in identifying the factors behind an accident, and their contribution to aviation safety is irrefutable. While not required by regulations, owners and operators should consider the benefits of installing such devices.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

Flight from Jandakot to Koorda

On 1 October 2022, a Robinson Helicopter Company R22 Beta II, registered VH‑RAS, departed Jandakot Airport, Western Australia for a private flight to an airstrip at Koorda (Figure 1 inset). The helicopter and several aeroplanes were being used to participate in a group social flying weekend, with the pilots and their passengers following a common itinerary but operating independently. The helicopter was being operated under the visual flight rules.[1]

The group arrived around midday at Koorda, and a witness recalled assisting the pilot of VH-RAS to fuel the helicopter with avgas[2] from 2 full 10 L plastic fuel containers, which they had been given by the pilot to drive to Koorda from Jandakot. This fuel was loaded into the main fuel tank. This witness also observed the pilot conduct a fuel drain during the pre‑flight inspection the next morning.

Return flight to Jandakot

On the morning of 2 October 2022, the group departed at staggered times from Koorda, on the return flight to Jandakot. VH-RAS departed at about 1140 local time, with the pilot and one passenger on board. It was reported that the pilot intended to refuel at Northam aerodrome, about 117 km to the south-west of Koorda. 

When VH-RAS did not arrive at Jandakot as expected, and after confirming it had not landed at Northam, the helicopter was reported as overdue at about 1500 and a search was commenced. The search was coordinated by the Australian Maritime Safety Authority’s Joint Rescue Coordination Centre. The wreckage was subsequently located at about 1600 on a dry salt flat in the Cowcowing Lakes region, about 13 km south-west of Koorda (Figure 1). The helicopter was destroyed, and both occupants were fatally injured. 

Figure 1: Flight from Jandakot to Koorda and from Koorda on the morning of the accident
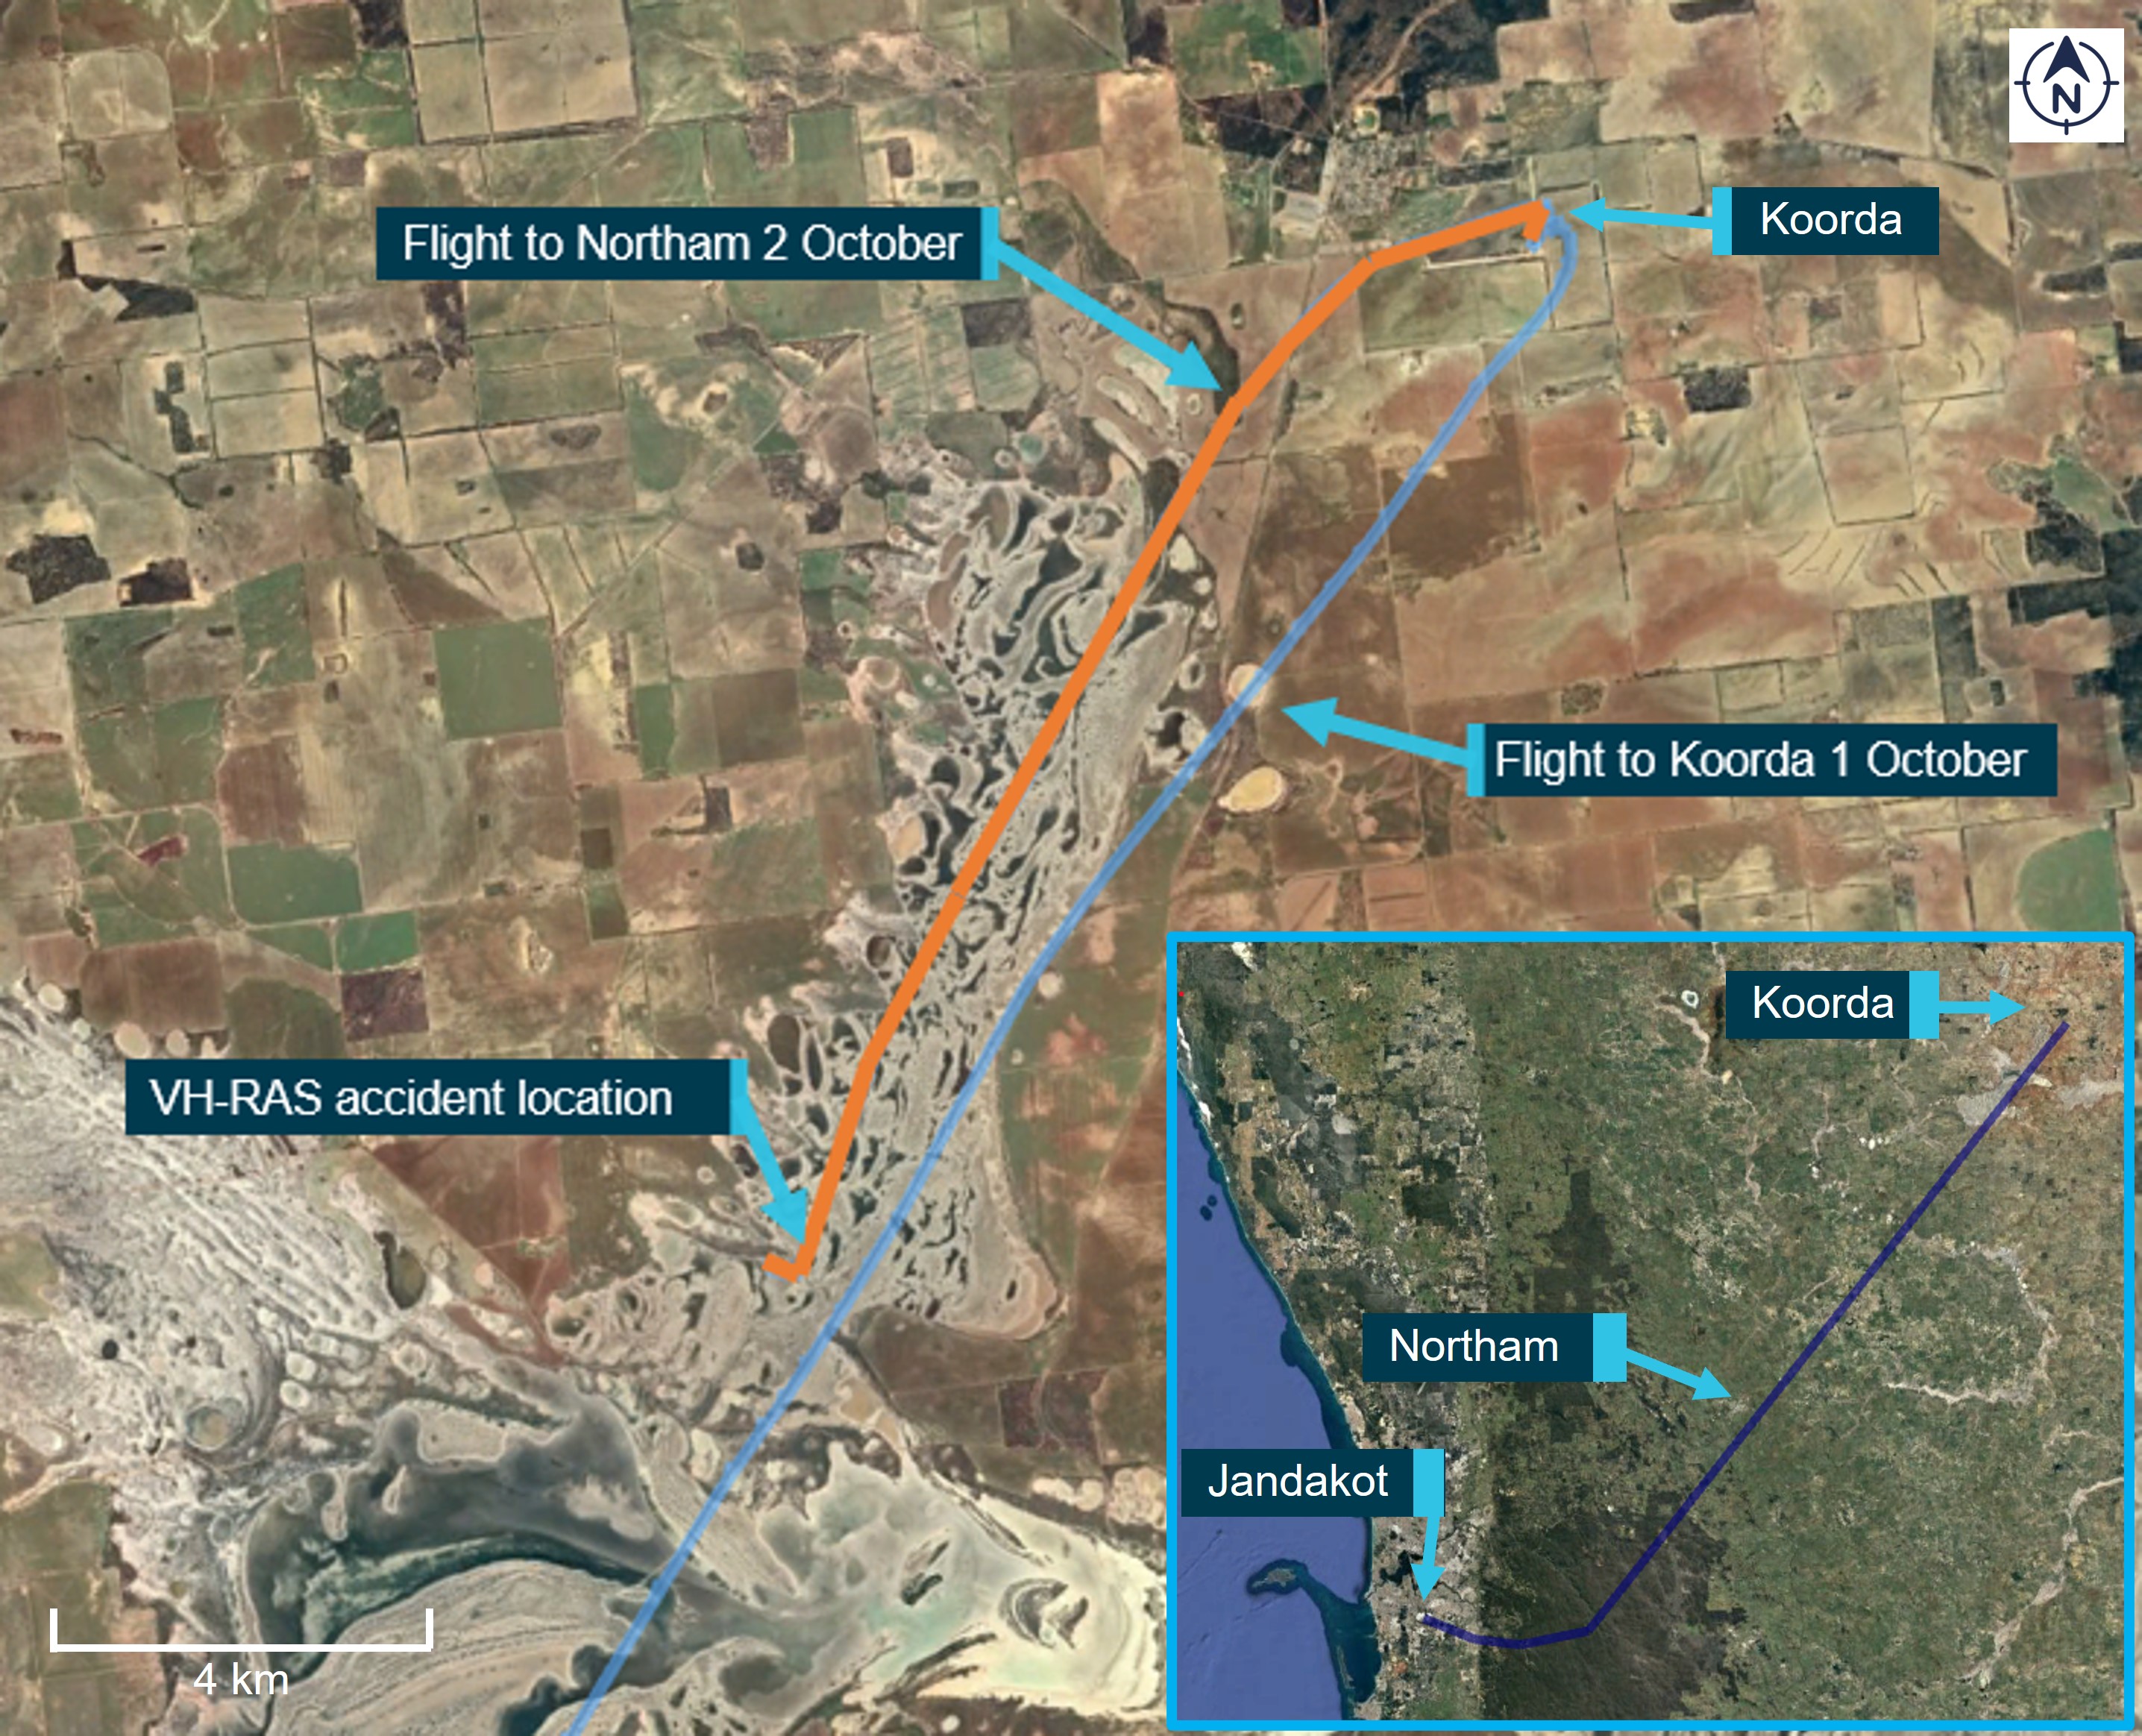
Figure 1: Flight from Jandakot to Koorda and from Koorda on the morning of the accident

Source: Google Earth and handheld GPS data, annotated by the ATSB

Context

Pilot information

General

The pilot was the owner of VH-RAS and held a private pilot licence for both aeroplanes (since 1976) and helicopters (since 2006). Their last flight review, conducted in VH‑RAS, was completed 11 January 2021. 

The pilot held a Class 2 Aviation Medical Certificate valid to 22 January 2024, which included restrictions requiring the wearing of distance vision correction and that reading correction must also be available while exercising the privileges of the licence. The pilot reportedly did not wear glasses while flying. However, their flight instructor and other pilots who flew with them, advised that they had not noticed any impediment with the pilot’s ability to operate the helicopter without wearing distance vision correction or at other times when reading the flight instruments.

Aeronautical experience

At their last medical in January 2022, the pilot reported that they had accrued about 3,000 hours total aeronautical experience (combined aeroplane and helicopter). It was also reported that the pilot no longer maintained their logbook, which prevented an accurate determination of their experience specific to aeroplanes and helicopters.

There were 16 entries on the current maintenance release, indicating the pilot typically flew the helicopter about twice per month, for about 20 minutes each time.[3] A review of previous maintenance releases determined that the pilot had operated the helicopter for a total of 77 hours since its purchase in 2016.[4] 

The pilot was reported to have regularly flown the helicopter accompanied by an experienced aeroplane commercial pilot and instructor, who also held a helicopter licence. Those flights would typically occur each month and involve about 45-minutes[5] of skill‑based flying practice, consisting of general handling, hovering, hovering turns and slope landing practice. No simulated emergencies or abnormal operations were practiced during those flights. In addition to those flights, they would do short flights to properties in the Perth hills or to nearby aerodromes to participate in social ‘fly-in’ breakfast events.

The pilot’s January 2021 helicopter flight review was performed by an experienced helicopter instructor and flight examiner who had conducted a significant amount of the pilot’s training and testing over the years. The flight review included simulated engine failures, autorotation[6] to confined areas, main rotor under speed recoveries and stuck tail rotor pedal emergencies. 

In addition to the flight review, the instructor recalled accompanying the pilot on other occasions during the period since January 2021. During this, the pilot had the opportunity to practice simulated emergencies under the instructor’s supervision.

The aviation community at Jandakot held the accident pilot in high regard and recognised them as somebody who had natural aptitude as both an aeroplane and helicopter pilot.

Recent history

The pilot was reported to typically retire to bed about 2100 and wake about 0500 most days. They were described consistently as being very health conscious, having exercised regularly and maintained very good overall health.

Members of the flying group that had spent time with the pilot during the weekend recalled them being their normal self, including prior to departing Koorda the morning of the accident. The pilot was reported to have slept normally, was well rested and had eaten breakfast with the group prior to arriving at the airstrip. There was no evidence to indicate the pilot was unwell nor experiencing a level of fatigue known to affect performance.

Passenger information

The passenger held a Student Pilot Licence (Aeroplane), with about 15 hours of flight experience in a Cessna Aircraft Company 152. They also held a valid Class 2 Aviation Medical Certificate, which included restrictions requiring the wearing of distance vision correction. It was stated that this was the passenger’s first flight in a helicopter. The passenger was reported to be well and that they appeared normal during the weekend, including prior to departing Koorda.

Helicopter information

General

VH-RAS (Figure 2) was a 2-seat Robinson Helicopter Company (RHC) R22 Beta II helicopter, serial number 4617, powered by a Textron Lycoming O-360-J2A, 4-cylinder carburetted piston engine. It was manufactured in the United States in 2013 and first registered in Australia the same year. It was purchased by the pilot in 2016 and had been maintained by the same maintenance organisation since that time. The helicopter was to undergo a periodic inspection every 100 hours or 12 months, whichever came first. The last periodic inspection had been completed in November 2021, with the current maintenance release issued at that time. At the time of the accident, the helicopter had accrued about 13 hours since the periodic inspection and 2,080 hours total time-in-service.

The helicopter was equipped with an intercom system and headsets, allowing those on board to talk to each other during flight. This would allow for clear communication between the pilot and passenger in the event of an abnormal situation. 

Figure 2: VH-RAS

Figure 2: VH-RAS

Source: Dallas Presser, modified by the ATSB

Rotor head design

The 2-blade main rotor assembly is a semi-rigid rotor head, otherwise known as a teetering rotor head (Figure 3). Bolts secure the rotor blades to the main rotor hub at the coning hinges.[7] The teetering head allows the rotor disk to take up an attitude appropriate to the flight condition, with the coning hinges allowing the blades to achieve the optimum coning angle appropriate for the flight and loading conditions. This design permits a lighter blade structure than would otherwise be required. 

During stopping and starting of the main rotor, when the revolutions per minute (RPM) are low, the spindle tusks rest against the droop stops, which are mounted near the top of the main rotor mast. The droop stops restrict the drooping of each blade to prevent contact with the tailcone at low rotor RPM. As the main rotor RPM increases, the blades become rigid and straighten due to rotational forces, and the tusks shift off the droop stop as the blades lift. During normal flight, the rotor is free to teeter and flap around its designed flight axis via the teeter hinge, while polyurethane teeter stops limit the degree of teetering to protect the mast from direct contact with the main rotor blades. The main rotor system is also fitted with pitch change links, which connect the swashplate to the pitch horn and transmit the flight control inputs to the main rotor blades.

Figure 3: R22 main rotor head assembly
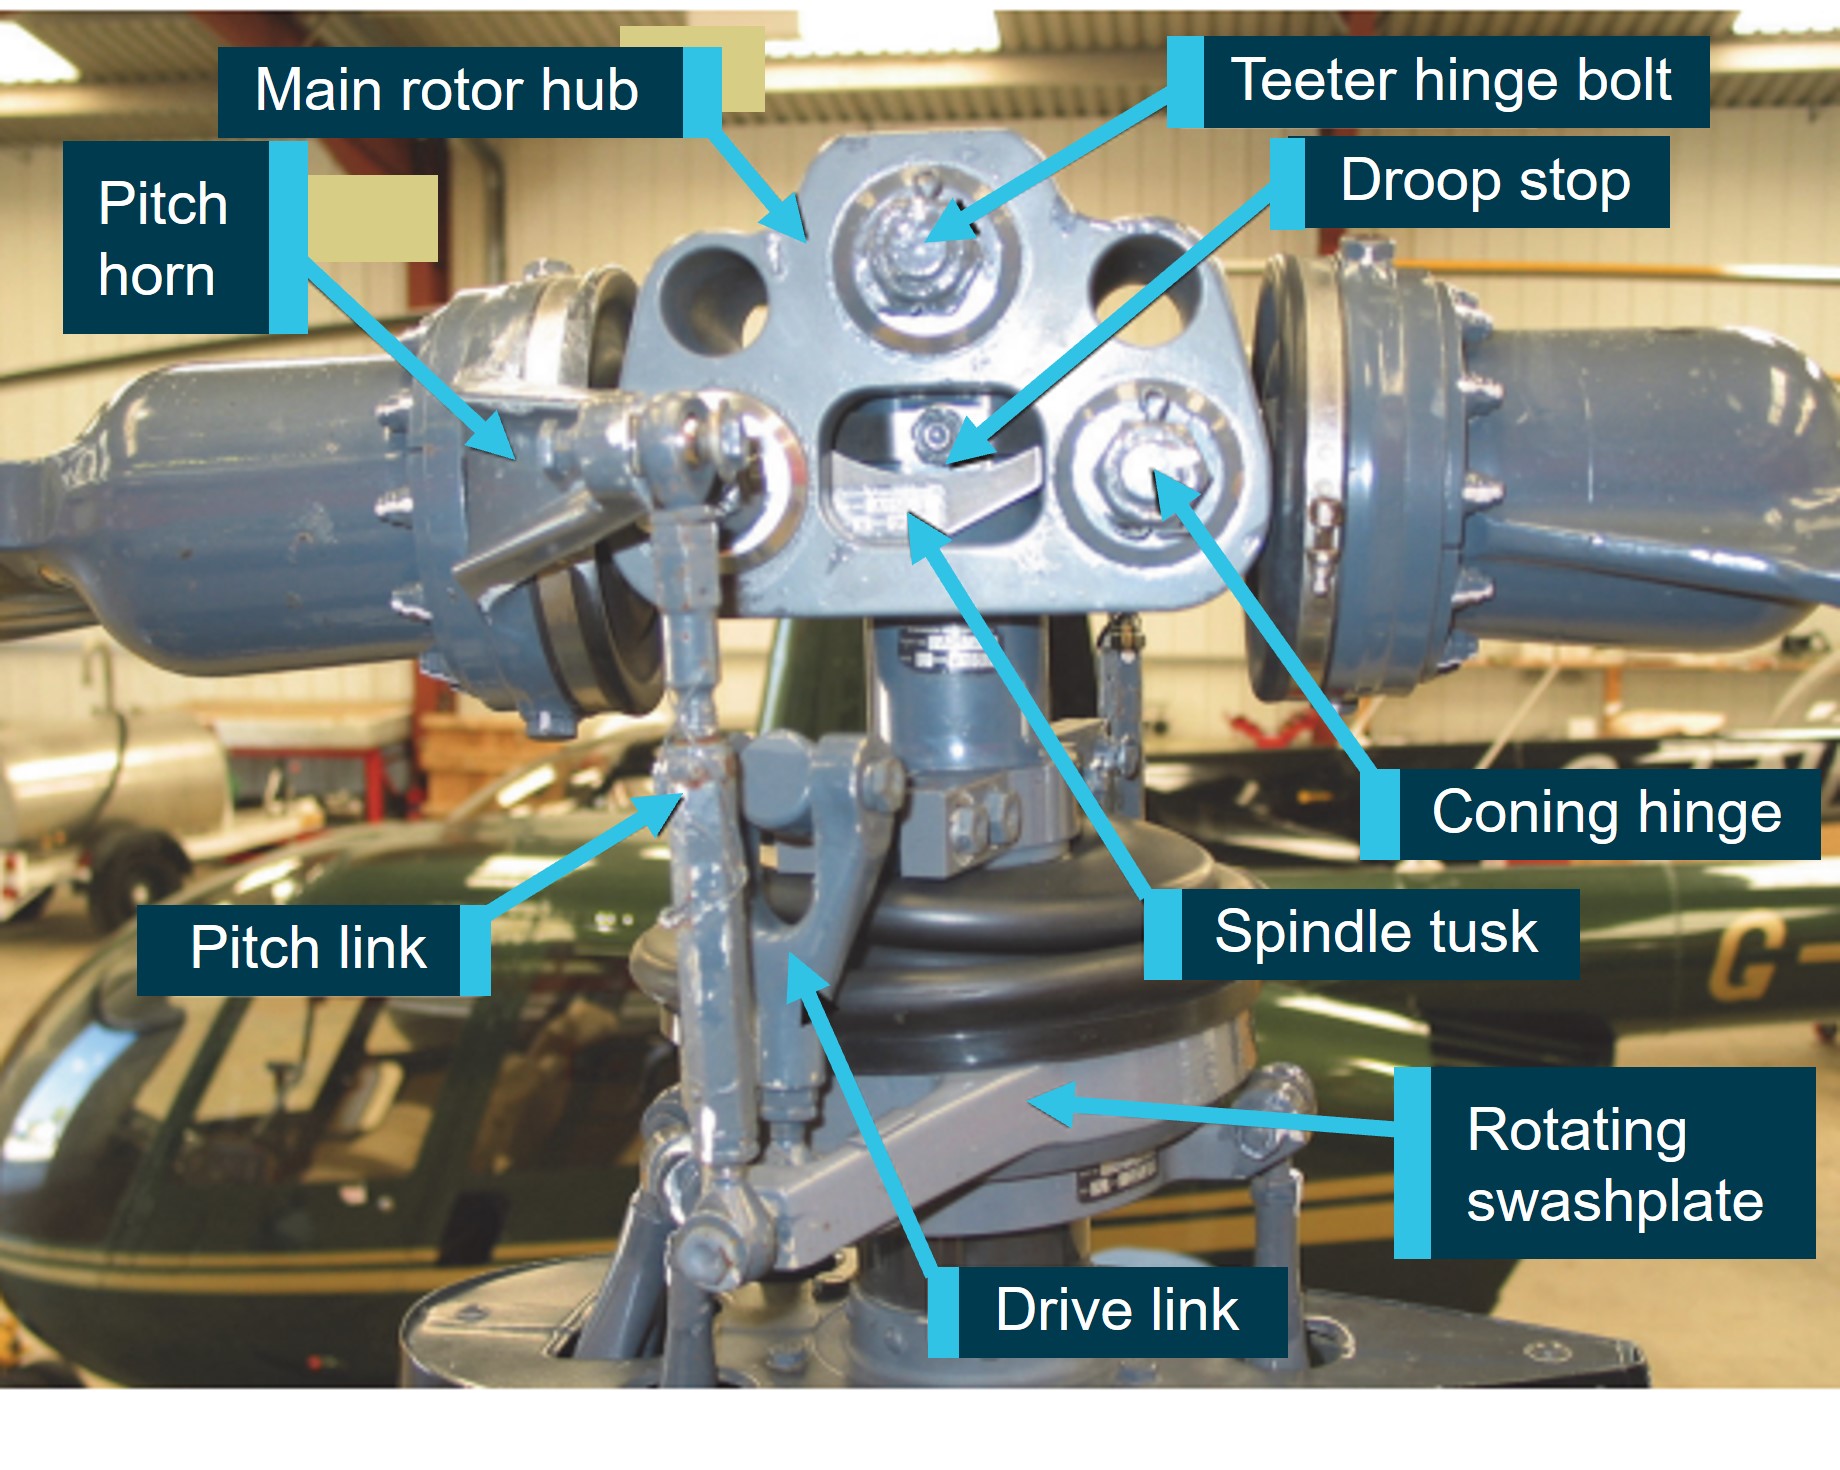
Figure 3: R22 main rotor head assembly

Source: United Kingdom Air Accidents Investigation Branch, annotated by the ATSB

Flight controls

The tail rotor pedals change the pitch of the tail rotor blades, and therefore the thrust of the tail rotor system, which provides directional control. The collective lever controls the amount of thrust (lift) produced by the main rotor disc. Raising or lowering the collective lever will raise or lower the swashplate,[8] which will alter the pitch on both main rotor blades to increase or decrease the main rotor thrust. The collective lever also incorporates a twist grip to provide the pilot with full manual control of the engine throttle. The cyclic[9] control tilts the main rotor disc to point the rotor thrust in the desired direction of flight. Fore‑aft movement of the cyclic provides the longitudinal (pitch) control of the main rotor disc. Left‑right movement of the cyclic provides lateral (roll) control of the main rotor disc. 

The helicopter was fitted with quick-disconnect dual flight controls (exemplar shown in Figure 4).[10] This consisted of duplicated collective and tail rotor pedal controls for both the pilot (right) and passenger (left) seating positions, and an additional control arm to the left of the T-bar cyclic control, enabling the cyclic control of the helicopter to be transferred between positions. In that configuration, the T-bar cyclic control would tilt down to be directly in front of the person controlling the helicopter. The opposite side cyclic control would still be connected and in front of the other seating position, but in a significantly higher position than normal (Figure 4 inset). The dual controls for the left seat position could be easily removed for passenger carrying operations. Notably, the R22 Pilot’s Operating Handbook (POH) included the caution: 

…remove left seat controls if person in that seat is not a rated helicopter pilot.

Figure 4: Dual flight controls, with insert showing deflection when being operated from the right 
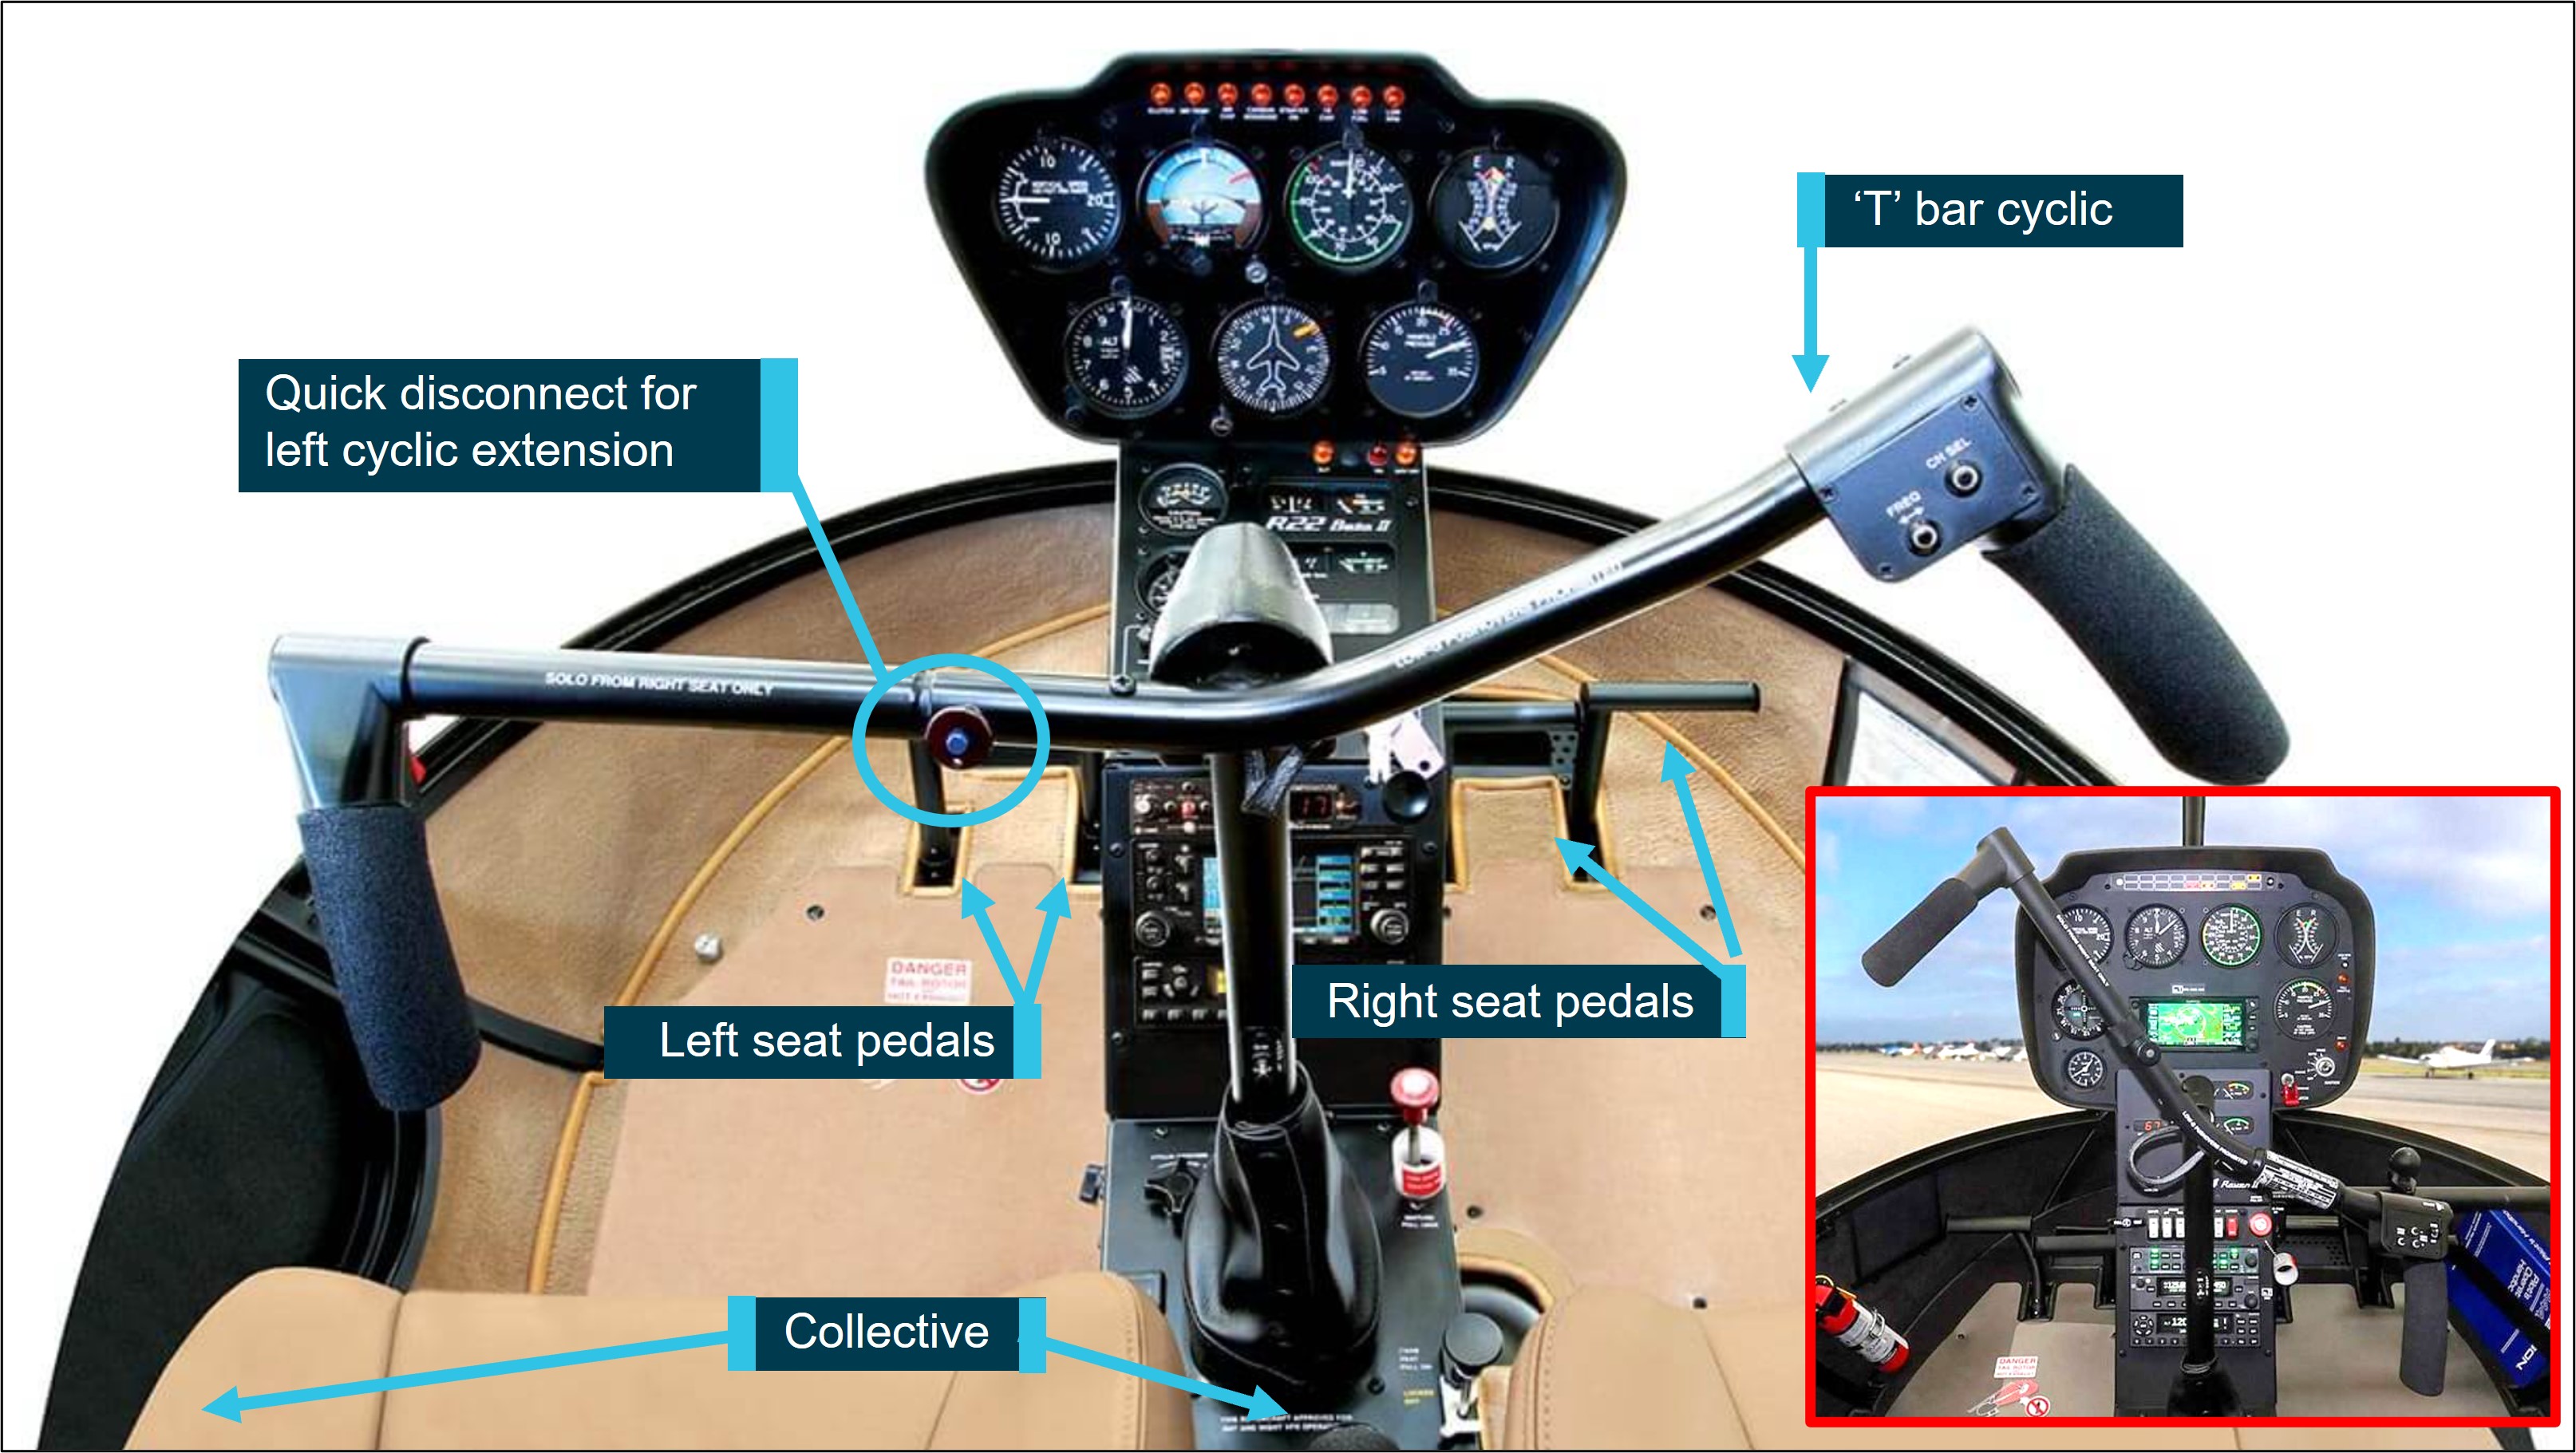
Figure 4: Dual flight controls, with insert showing deflection when being operated from the right

Note: While the insert image is from a R44 helicopter, it demonstrates the position of the opposite cyclic grip when the T-Bar is oriented to the pilot sitting in the right seat, with similar see-saw orientation when being held by the left seat pilot.

Source: Robinson Helicopter Company, annotated by the ATSB

Fuel system

The fuel system consists of a main tank (left side, 69 L) and an auxiliary tank (37 L, right side). Fuel is gravity-fed (no pumps) via the gascolator to the carburettor.

Engine governor system

Under normal conditions, the governor senses engine RPM and makes adjustments to the throttle control to maintain a constant engine RPM, which leads to a constant rotor RPM in flight. It can be selected on or off using the toggle switch on the right seat collective. The POH stated that the governor may not prevent over- or under-speed conditions generated by aggressive flight manoeuvres. In the event of malfunction, the pilot can override the governor and manipulate the throttle to maintain engine RPM, until the governor can be selected off, or rendered inoperative by pulling the circuit breaker.

Carburettor heat system

The helicopter was fitted with a carburettor heat system, which directed hot air collected from a scoop installed on the engine exhaust system, via a duct, to the engine induction air box. Within the airbox was a sliding guillotine-type valve to proportion the mix of cool and heated air. The pilot could monitor the temperature of the carburettor air using the carburettor air temperature gauge on the instrument panel console.[11] The carburettor heat control knob was situated aft and rear of the cyclic, with ‘down’ being no heat and ‘up’ providing full heat, or anywhere in between as selected by the pilot. This heated air prevented the temperature within the carburettor from dropping to at or below the freezing point of water. While the increase in carburettor air temperature would result in a small reduction in power, this could be countered by increasing throttle and manifold pressure.

The helicopter also had a carburettor heat assist system, which automatically applied carburettor heat when lowering the collective, generally for descent, to reduce pilot workload. The pilot could override the heat assist. In addition, a latch was provided at the carburettor heat control knob to lock the heat assist off when not required.

Weight and balance

Weight and balance for the accident flight was calculated using the approved weight and balance record, together with the estimated fuel load, occupant weights and recovered luggage. To calculate the fuel on board departing Koorda, the ATSB used scenarios where the helicopter was fully‑fuelled prior to departing Jandakot and the average fuel consumption (as specified by RHC) was between 7 and 10 US gallons per hour (26–38 L/hr). Using those rates, the ATSB estimated that, on engine start at Koorda, the helicopter had between 40‑54 kg (55–75 L) of fuel onboard, which included the 20 L added the day before.

Irrespective of the fuel load departing Koorda, the helicopter’s lateral and longitudinal centre of gravity remained within the limits published by the manufacturer. However, the helicopter would have been at about its maximum gross operating weight if departing Koorda with 40 kg of fuel but could have exceeded the maximum gross weight by about 15 kg if departing with 54 kg of fuel. Despite this, as the helicopter was observed to have departed normally, and reached a cruise altitude, this would suggest that the overall weight did not significantly reduce the helicopter’s performance.

Meteorological information

Bureau of Meteorology forecast and analysis

The graphical area forecast prepared by the Bureau of Meteorology indicated visual meteorological conditions[12] were expected during the flight to Jandakot. Winds were forecast to be generally east-south-easterly below 5,000 ft above mean sea level, between 15–20 kt. There were no SIGMET[13] or AIRMET[14] warnings applicable to the flight.

An analysis prepared by the Bureau of Meteorology indicated a high-pressure system was situated to the south‑west of Western Australia, producing moderate east to south‑easterly winds in the vicinity of the accident site. Satellite imagery and measurements from the weather station at Cunderdin (about 80 km south of the accident site) indicated there was scattered cloud[15] in the vicinity of the site, with bases approximately 4,500–5,000 ft. There was the possibility of some thermal turbulence as the surface temperature and cloud base increased during the day, with a well-mixed air layer below the cloud. However, the analysis did not identify the existence of any hazardous weather phenomena in the vicinity of the accident site.

The air temperature at 2,500–3,000 ft was estimated to be about 10–12 °C, with a dewpoint[16] of about 6–8 °C. According to the Civil Aviation Safety Authority Carburettor icing probability chart, this temperature and dew point were within the ‘serious icing – any power’ envelope.

Pilot reports

Pilots of the other aircraft in the group reported good flying conditions during the flight back to Jandakot. Those reports were generally consistent with the Bureau of Meteorology’s analysis. There was slight variation in the pilots’ estimates of the cloud bases during their flights, ranging between 3,000–4,500 ft. Several pilots who departed Koorda that morning reported encountering some turbulence over the Cowcowing Lakes area. Most described the turbulence as mild, but one pilot reported an instance of ‘moderate’ turbulence,[17] an updraft of sufficient magnitude to startle their passenger and dislodge loose items in the cockpit. 

Recorded information

The helicopter was not fitted with a cockpit voice recorder, flight data recorder or cockpit camera, nor was it required to be. Neither the pilot nor the passenger’s mobile telephones were identified at the accident site.

Sources of data

A handheld GPS receiver and lanyard was recovered at the accident site and data was successfully downloaded. A review of the data found that during the accident flight, data was recorded at intervals varying between 1 and 19 seconds, with shorter intervals representing periods where the track and speed calculated by the GPS was rapidly changing. The information logged included GPS-calculated position, track, groundspeed, and altitude. 

While no mobile telephones were found, the passenger was using the OzRunways[18] application installed on their iPhone during the flight. The application was using the mobile telephone network to transmit data to the OzRunways’ servers every 5 seconds, which included the current position, track, groundspeed and truncated altitude in increments of 100 ft.[19]

Correlation of data

There was a strong correlation between the track log from the handheld GPS and the data transmitted by the iPhone to the OzRunways’ servers. The only significant discrepancies were during the initial climb with the handheld GPS-calculated altitude lagging behind the altitude data transmitted from the iPhone and during the last 10 seconds of recorded data (altitude, groundspeed, and position). Analysis of the last 10 seconds of data indicated several of the positions calculated by the handheld GPS required groundspeeds that exceeded the helicopter’s performance capabilities. During that period, any rapid changes in the satellite constellation used by the GPS could adversely affect the accuracy of the calculated position. The position calculated by the iPhone used additional sensors and GPS frequency bands, and those positions were more consistent with the helicopter following that trajectory during the descent.

Analysis of recorded data 

The elevation of Koorda airstrip was about 1,060 ft above mean sea level. The handheld GPS started recording position information at 1136:32 local time. At 1139:50, the track log of the GPS indicated that the helicopter was airborne and on initial climb. Soon after, the OzRunways application on the iPhone started transmitting data, also consistent with the helicopter being airborne.

There was a close correlation between the 2 tracks and groundspeeds. The helicopter’s airspeed during the initial stages of climb was estimated to be between 60 and 65 kt,[20] which was consistent with the helicopter manufacturer’s recommended climb speed. The estimated airspeed increased progressively towards about 80 kt during the latter stages of the climb. About 3 minutes 40 seconds after take-off, the iPhone and GPS altitude stabilised at about 2,700 ft (refer Appendix A for graphed data).

During the latter stages of the climb and the initial cruise, the pilot’s tracking of the helicopter towards Northam closely matched the track required[21] and any track error was generally less than 5°. This was similar to the tracking performance achieved by the pilot during the outbound flight on the previous day.

About 1 minute after reaching 2,700 ft, the tracking accuracy towards Northam began to reduce (measured as the calculated difference between the track required and track made good).[22] About 20 seconds later (1144:48), the altitude indicated by the iPhone had increased by a 100 ft increment to 2,800 ft (and the handheld GPS altitude also increased by a commensurate amount), with an estimated airspeed of 83 kt. 

About 45 seconds after reaching 2,800 ft and with an airspeed of about 76 kt (at 1145:33), the iPhone data indicated that the helicopter had departed abruptly from controlled flight, descending from 2,800 ft to 1,300 ft over a 10-second interval (a rate of descent of about 9,000 ft/min). The helicopter subsequently collided with terrain (at an elevation of 930 ft), about 6 minutes after becoming airborne at Koorda. 

Data transmitted by the iPhone (blue) and data from the handheld GPS (green) is depicted in Figure 5 and Figure 6.

Figure 5: Correlated track data for VH-RAS from Koorda to the accident site
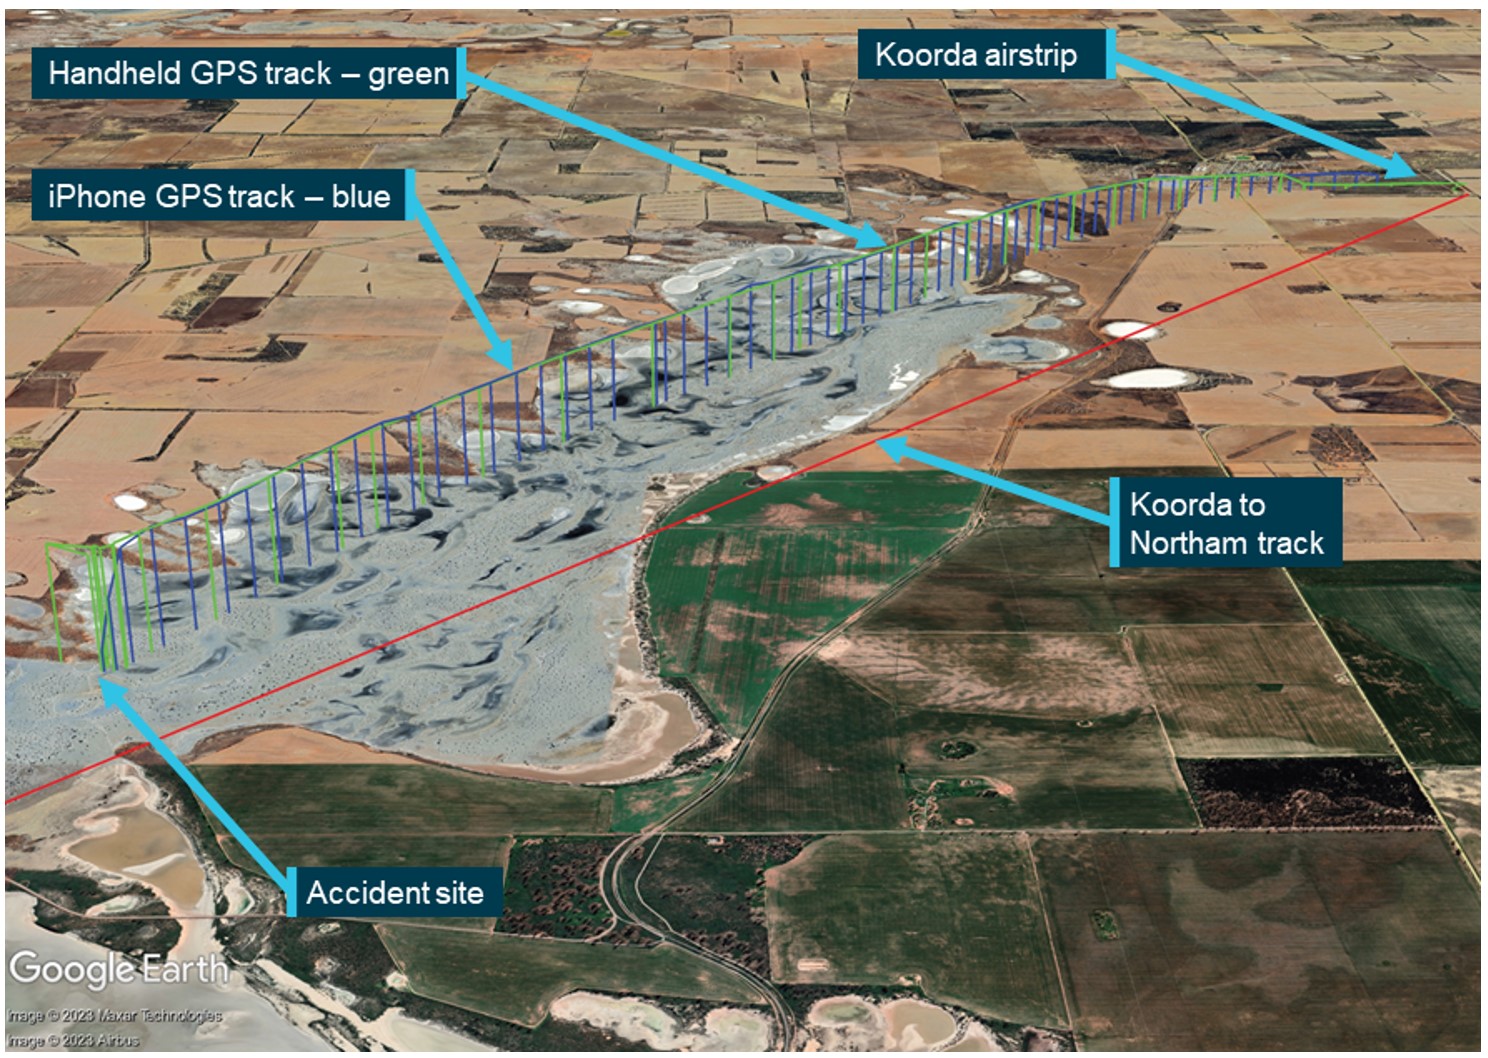
Figure 5: Correlated track data for VH-RAS from Koorda to the accident site

Source: Google Earth, annotated by the ATSB 

Figure 6: iPhone track data, truncated altitude, and estimated airspeed for VH-RAS during last the 2 minutes of flight
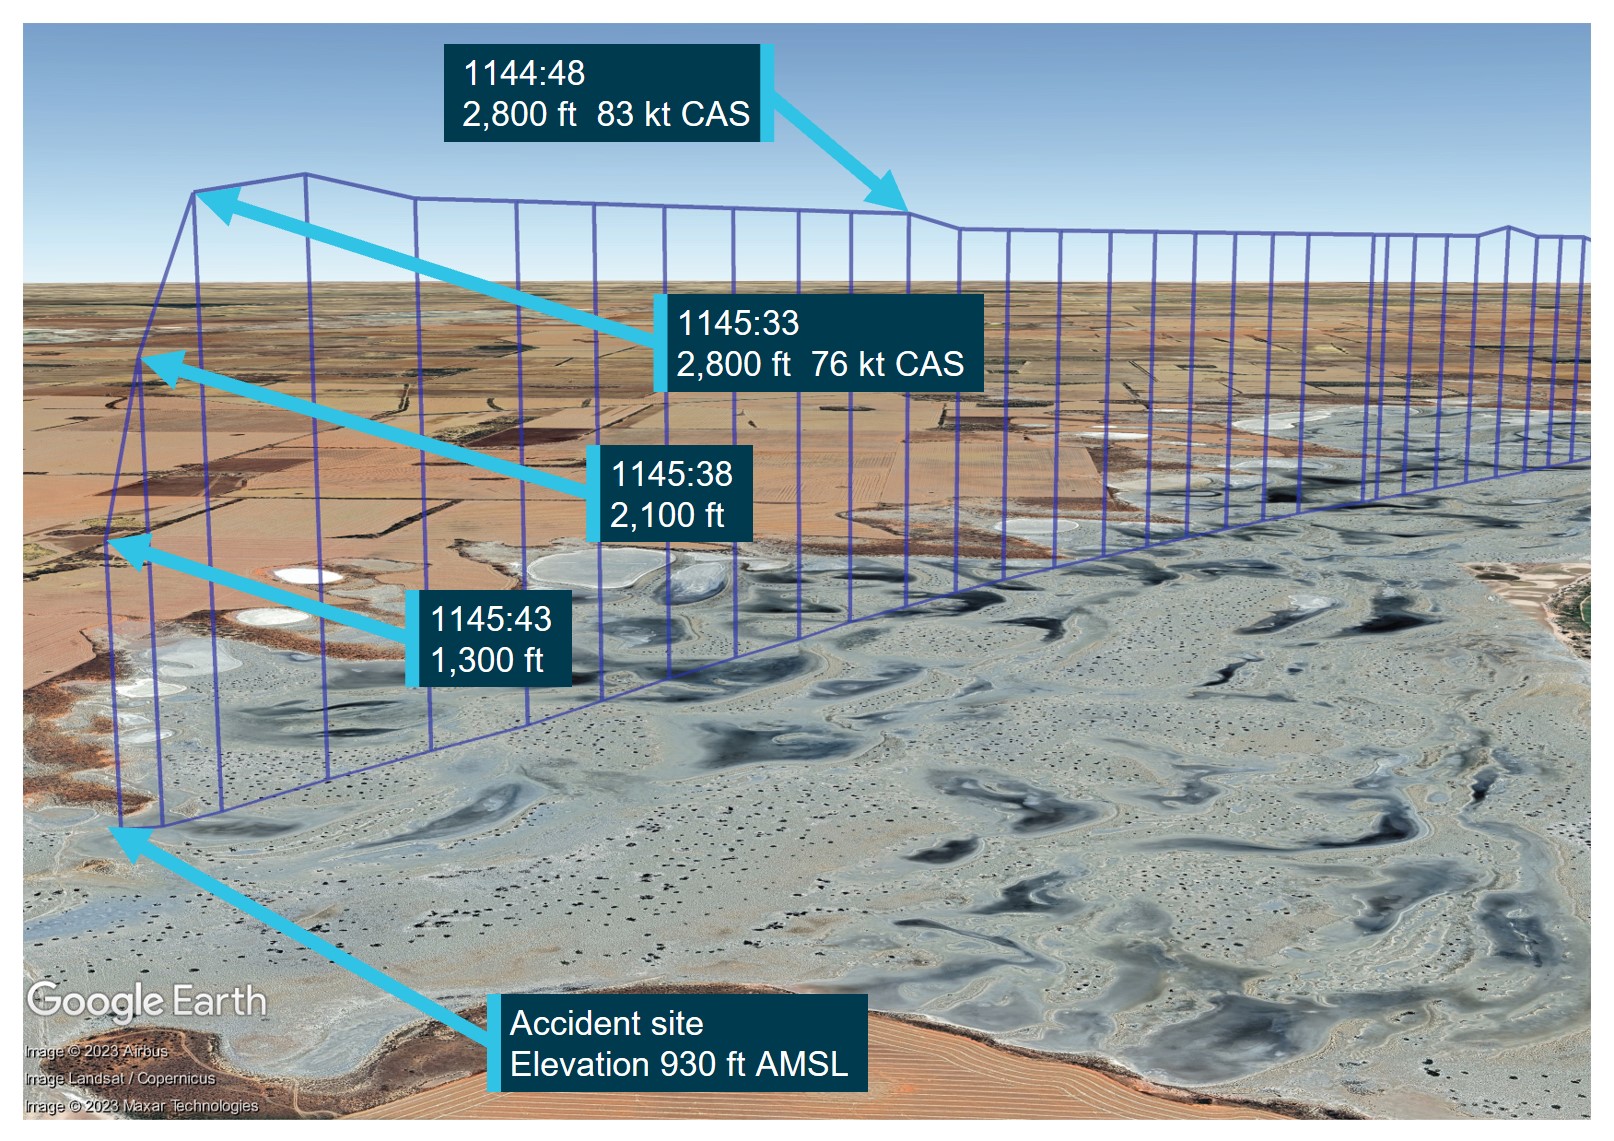
Figure 6: iPhone track data, truncated altitude, and estimated airspeed for VH-RAS during last the 2 minutes of flight

Source: Google Earth, annotated by the ATSB 

Helicopter onboard camera

RHC introduced cockpit video cameras, which have been standard on new R66 and R44 helicopters since early 2021 and 2022 respectively and are an optional retrofit to in-service helicopters of both types. At the time of publication of this report, it remained optional for new R22 helicopters, with retrofit available to most in-service R22s. The forward-facing camera records video (encompassing a view through the windshield, pilot controls and the instrument panel), intercom audio, radio transmission and GPS data. RHC advised the recordings (up to 10 hours) can be used as a training tool, maintenance aid, or aerial-tour souvenir. 

The recording could also assist with occurrence investigations by allowing investigators to understand the circumstance/s that precede an accident, particularly when there are no survivors or witnesses. In turn, this aids the identification of important safety issues.

Wreckage and impact information

Wreckage distribution

The helicopter collided with terrain inverted, on a dry salt flat, on an easterly heading. A small distance below the salt crust was loose muddy sand and the water table was close to the surface. The main rotor head, with blades attached, and the top portion of the mast had separated but were located alongside the fuselage (Figure 7). One main rotor blade had fractured, with the outboard section located about 3 m from the main rotor assembly. The tailcone, including the tail rotor assembly, was attached to the fuselage. The horizontal and vertical stabiliser assembly had separated and was located about 6 m from the tailcone. The auxiliary fuel tank bladder was intact, however, the main tank bladder had ruptured due to impact forces. There was no fire.

Distribution of the wreckage and ground scars were consistent with an almost vertical descent and little to no rotation of the main rotor blades. Both occupants were found secured in their respective restraints, however, due to the high descent rate and inverted orientation, the impact was not considered survivable.

Figure 7: Accident site and wreckage
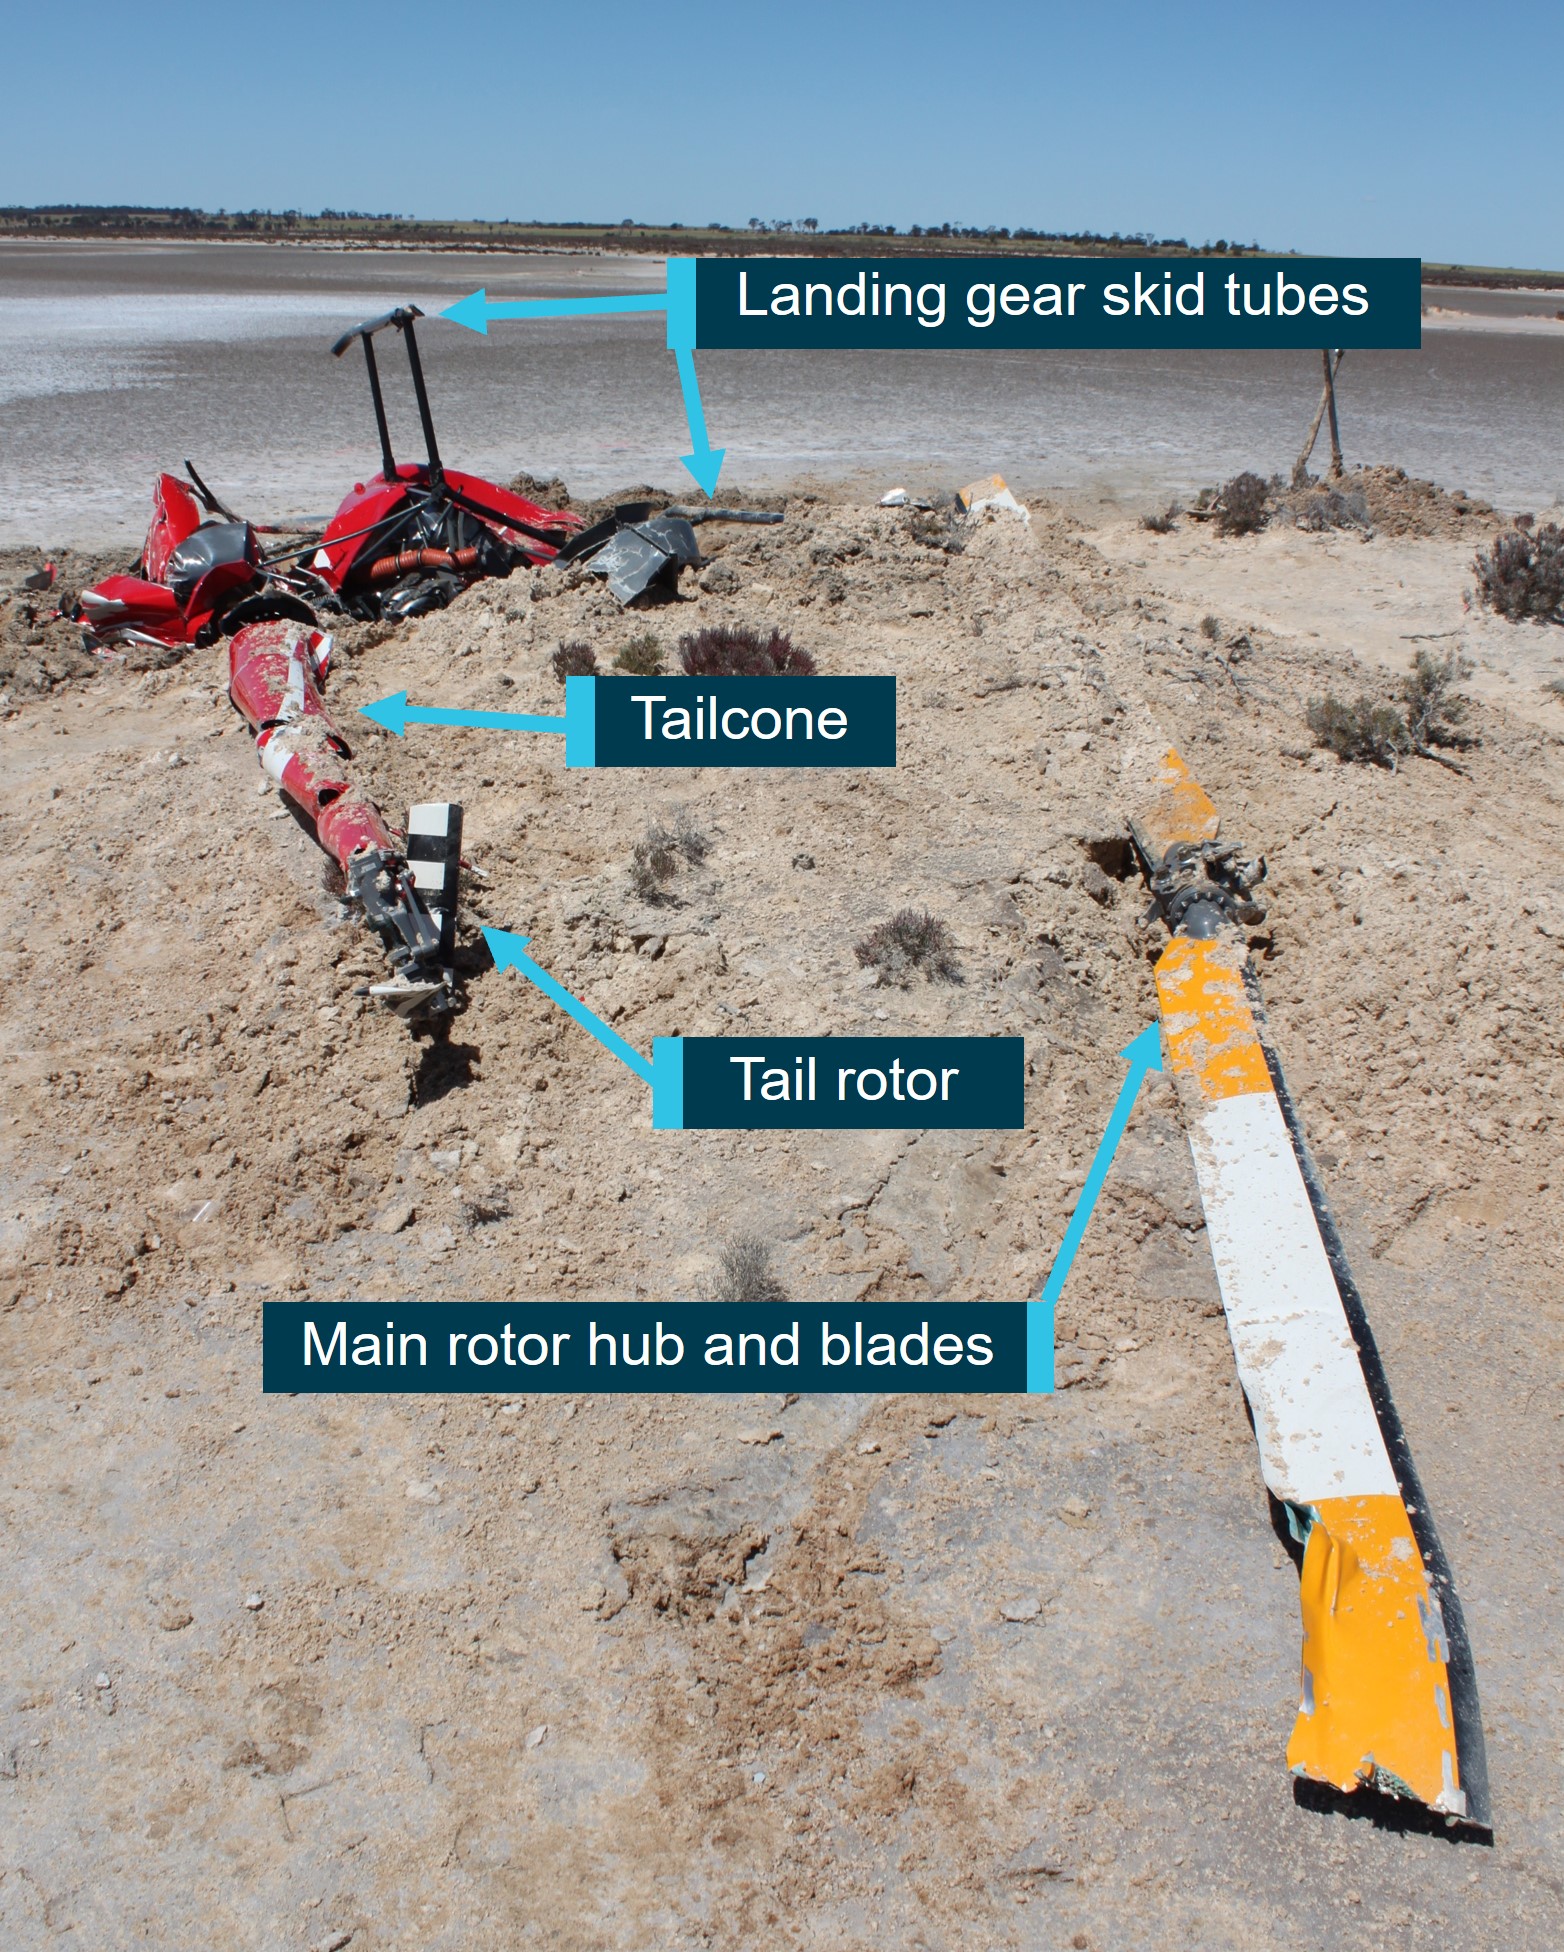
Figure 7: Accident site and wreckage

Source: ATSB

Wreckage examination

Detailed examination of the wreckage identified continuity of the flight and engine controls, with all fractures consistent with overstress failure, however, distortion to the fuselage precluded determining engine control position prior to impact. There was nil evidence of birdstrike found in the wreckage or the surrounding area. The examination further identified the following:

Powerplant

There was no evidence of a restriction or blockage to any part of the air induction system. Notably, the air intake SCEET hose[23] was in good condition with nil delamination and the air box filter was clear. The governor switch (located at the end of the right seat collective) was in the OFF selection. Although this may not necessarily reflect the position of the switch prior to the accident due to the damage sustained to the helicopter during the impact sequence. In addition, the governor circuit breaker was noted to be in the operational selection (not pulled due to failure or troubleshooting). 

The carburettor heat selector was fully down (no heat) and the carburettor heat assist lockout latch was unlocked. However, it was possible these positions were altered during the impact sequence. Therefore, the actual positions prior to the impact could not be determined. The air box carburettor heat slider was about mid travel, but impact forces and fuselage distortion pulled the control cable, preventing determination of the pre-impact position. Some scoring to the alternator fan backing plate and oil cooler was indicative that the engine may have been rotating at impact, although the damage was not consistent with the engine operating at full power.

Drivetrain

There was no evidence of pre-existing defects to the drive shafts, drive belts or sheaves. The drive belt tensioning clutch actuator had fractured in overstress, however, the actuator setting was consistent with normal operation and stretch of in-use belts. The main rotor transmission case had fractured open on the forward right side, but there was no evidence of failure of the transmission internal gears. The ATSB could not determine if the fracture was sustained during extreme teetering (refer to section titled Extreme teeter and mast bumping) or the impact.

Main rotor system

Damage to the main rotor head components (refer Figure 8 for main rotor head components detail) included:

  • both main rotor pitch change links had fractured, in overstress, at the upper rod end thread 
  • both spindle tusks had fractured and the tusks were not recovered
  • the teeter stops had fractured in the centre due to severe impact forces from the spindles, the lower halves had been liberated and impact damage was visible on the mast. 

The mast had fractured near the swashplate, with no evidence of pre-existing fatigue. The fracture location was coincident with impact from a pitch horn that was free to rotate down and impact the mast, following pitch link failure. The fractured main rotor blade exhibited red paint transfer and damage consistent with it striking the forward fuselage with low energy and wrapping under the cabin.

Figure 8: Main rotor head and mast damage
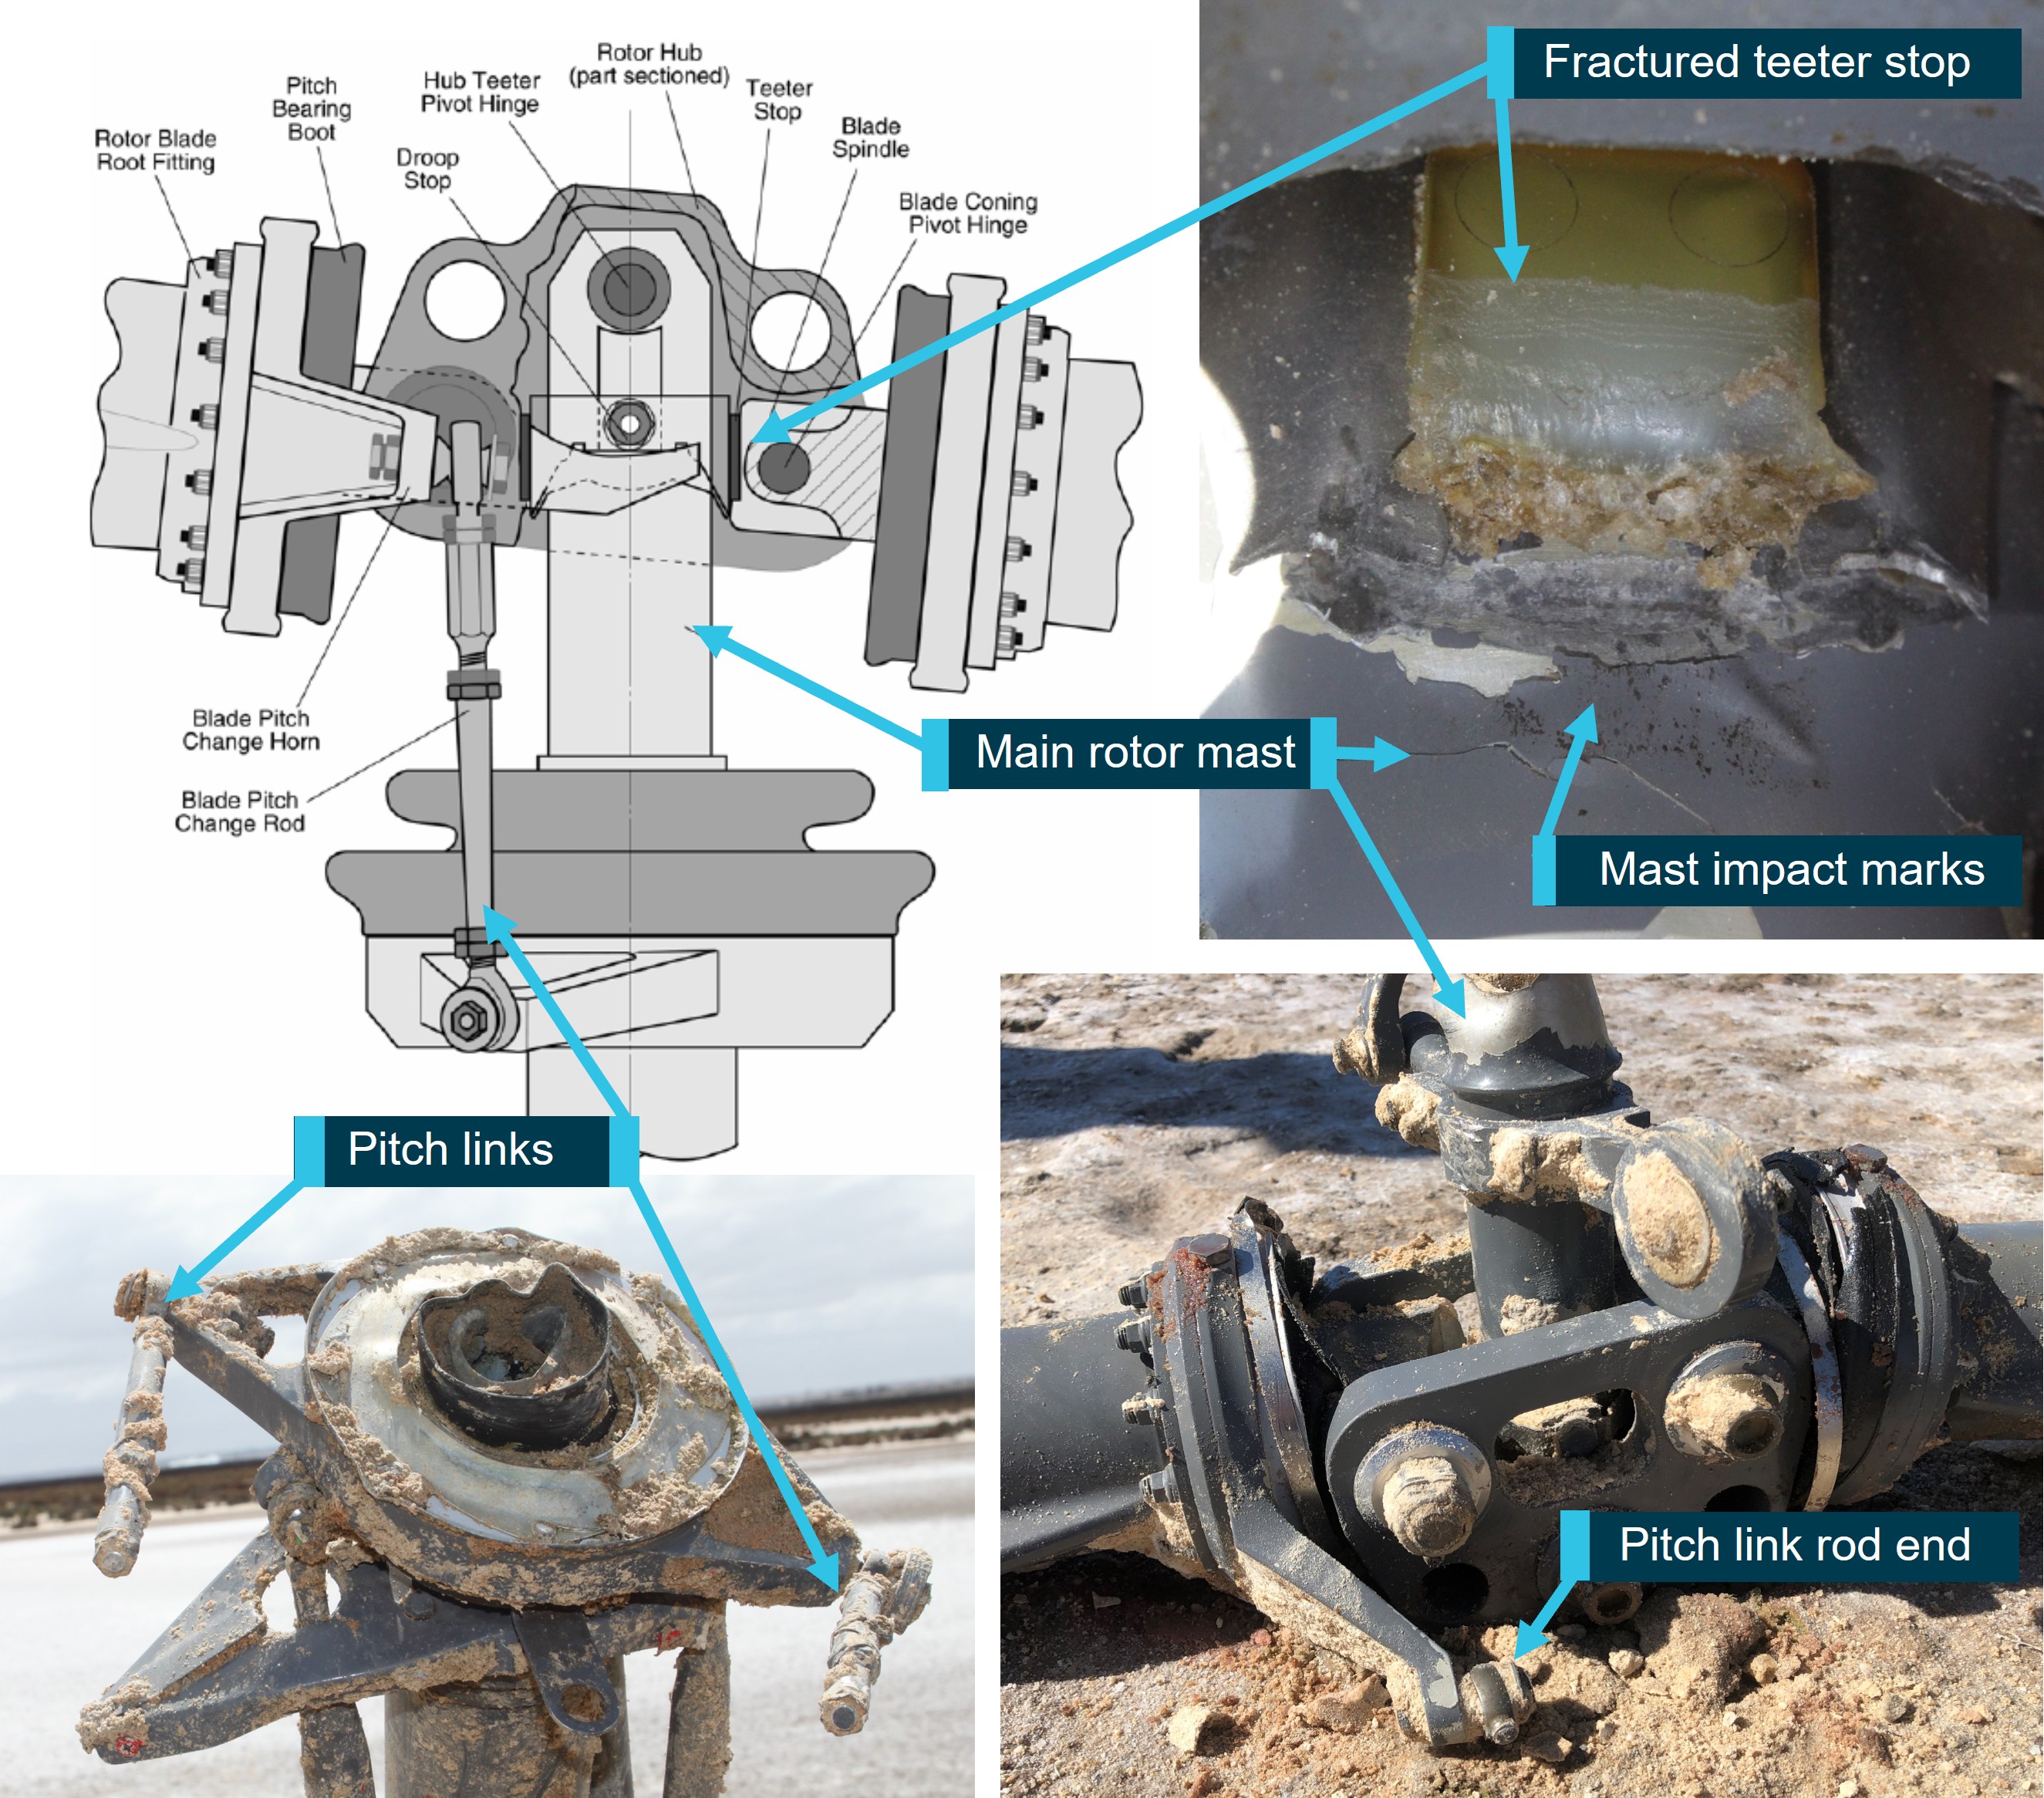
Figure 8: Main rotor head and mast damage

Note: Diagram of typical R22 main rotor head showing VH-RAS fractured pitch links and corresponding rod end, teeter stop split in half and impact damage from mast bumping.

Source: ATSB and the United Kingdom Air Accidents Investigation Branch

Fuselage and cabin 

Both windshields had shattered, however, the bow (central pillar) was intact. The left seat quick‑disconnect dual flight controls were installed. It was reported both doors were fitted when the helicopter departed Koorda.[24] The left door or its components were not identified in the wreckage at the site, nor in an extensive search of the surrounding area. It was possible it may have been destroyed during the main rotor blade strike to the cabin, but with the fragments unable to be identified or located in the loose muddy sand that was below the salt crust. There was no evidence of main rotor blade strike to any portion of the tailcone.

Post on-site examination

The governor controller was sent to the helicopter manufacturer in the United States for testing, observed by the ATSB (via video link). However, impact damage prevented any functional testing. An internal visual inspection revealed damage consistent with impact forces and there was no evidence of electrical arcing or overheating of the circuit board components.

The ATSB collected a small amount of fuel from the gascolator and auxiliary tank. This was tested by an independent accredited laboratory. While the fuel recovered had been contaminated with ground water after the collision with terrain, the fuel content was consistent with 100 LL Avgas.

Most of the lamps for the warning and caution lights, including low rotor RPM, low fuel and engine governor-off, had been destroyed by impact forces. The only lamps available for testing (clutch, alternator, main rotor chip and main rotor temperature) were examined at the ATSB’s technical facilities in Canberra, Australian Capital Territory. The main rotor chip and temperature lamp filaments had fractured and there was no observable stretch.[25] Examination of the alternator[26] and clutch[27] lamps indicated they probably were illuminated at impact. However, it was unknown if these indications would have illuminated prior to, during, or as a result of the impact sequence. Therefore, the status of these lights prior to the impact was unable to be determined.

In addition, examination of the instruments identified possible contact transfer of material from the needle to the instrument face, at 50-55% engine and 58% rotor RPM on the dual tachometer. The normal operating range for the engine was 101% to 104%, with a maximum continuous RPM of 104%. The engine RPM had to be maintained within this tolerance for the main rotor system to provide effective lift. A possible sweep mark at 11‑15 inches of mercury was identified on the manifold pressure gauge, which was lower than would be expected in cruise conditions. This could be indicative of severe icing, however, it was also possible that the sweep between 11 and 15 was from disruption due to impact forces. There were no reliable marks identified on the carburettor air temperature gauge face or internal components.

In early November 2022, the engine was disassembled and examined at a Civil Aviation Safety Authority (CASA) authorised engine overhaul facility under the supervision of the ATSB. The engine condition was consistent with the engine’s recorded time-in-service since overhaul. No internal or external damage was identified that may have prevented the engine from operating normally prior to the accident. No defects were identified in the induction system components, core engine, or cylinder assemblies that may have affected its pre-accident operation. One magneto was operationally tested with positive results, however, the other could not be tested due to impact damage. Both magnetos were also internally examined, and resistance tested with nil defects identified. Further, the carburettor was bench tested and internally examined, with no issues identified.

In summary, examination of the helicopter’s flight and engine control systems, drive train and powerplant did not indicate any pre-existing defects that may have affected the control or normal operation of the helicopter.

Medical and pathological information

Post-mortem examinations

A full post-mortem examination was performed on the pilot and a limited examination conducted on the passenger.[28] Within the limits of this examination, the pilot’s post‑mortem did not identify any significant natural disease.

The post-mortems identified multiple fractures and injuries to both the pilot’s and passenger’s arms, hands, and legs. Research has previously been conducted into injuries sustained by control seat occupants during an accident and the extent to which those injures would be consistent with the occupant of the seat having their hands or feet on the controls. However, some research has found that the passenger and pilot may exhibit similar injuries if the passenger grasps a solid structure, such as bracing in anticipation of an impact (Cullen, 2004; Gradwell and Rainford, 2016). In addition, the inverted impact with terrain and limited protection provided by the lightweight airframe could have also contributed to the nature of the injuries sustained. Therefore, the evidence was inconclusive in determining whether the pilot or the passenger was manipulating the flight controls. Further, it could not be established if either had a medical event that prevented the other from being able to maintain control of the helicopter.

Toxicology testing conducted on pilot

Toxicology testing conducted as part of the pilot’s post-mortem examination detected the presence of paracetamol, propranolol, and quinidine/quinine. Carbon monoxide detected in the samples was less than 5%.[29]

Paracetamol is a commonly used over the counter analgesic, but generally without adverse side effects significant for its use in aviation. Propranolol, quinine and quinidine are prescription medications with some potential side effects and interactions.

A review of records from the Pharmaceutical Benefits Scheme, from June 2018, indicated that the pilot held prescriptions and a dispensing history for propranolol and temazepam, but none for either quinidine or quinine.

Quinidine and its naturally occurring stereoisomer (mirror image) quinine are natural alkaloids[30] and are individually synthesised for pharmaceutical and medical purposes. The toxicology testing technique could not differentiate between the 2 compounds. Quinidine was typically used to treat heart arrythmias and quinine, as a pharmaceutical medication, to treat malaria. Quinine is also used as a bittering agent in soft drinks such as bitter lemon or tonic water. The pilot used tonic water as a mixer with alcoholic drinks but was reported to have not consumed any during the days prior to the accident.

Propranolol is a prescription medication in the Beta-blocker class of drugs, that blocks the release of stress hormones, such as adrenaline. It can be prescribed for a variety of conditions that include migraines, benign heart palpitations and performance anxiety. The use of propranolol in an aeromedical context is discussed below (refer to section titled Civil Aviation Safety Authority review of propranolol use).

Consultant pharmacologist review

The ATSB engaged a consultant pharmacologist to review the results from the pilot’s toxicology testing. That review found the level of propranolol detected was unlikely to have been consumed during the period 24-hours prior to the accident, nor did they anticipate any adverse effects on the pilot’s ability to operate the helicopter during the accident flight.

They also concluded that if the quinine or quinidine source was from tonic water (ingested as quinine), it would have most likely have had to be consumed within the previous 24 hours and at the detected levels, they would not have expected any impairment of the pilot’s performance. If the source was quinidine (as a medication), it could have been consumed during the previous few days.

Further, the consultant pharmacologist found that the carbon monoxide levels (less than 5% saturation) in the non-preserved blood of the pilot was insignificant.

Civil Aviation Safety Authority review of propranolol use

Although propranolol was not a medication prohibited for use by pilots, the reason for its use could be of aeromedical significance and for that reason, required assessment by a designated aviation medical examiner (DAME) and/or CASA. Aeromedical impacts for its use included the blocking of the effect of adrenaline in maintaining blood pressure under g‑loading and to also reduce blood pressure at normal g-loadings but making the pilot more prone to light headedness from other causes such as dehydration.

Due to the potential side effects, CASA advised the ATSB that propranolol would not usually be approved for pilots who were likely to encounter high g-loadings[31] (high performance aircraft) or operations involving complex variations in g-loadings (push-pull effects in particular). In other cases, pilots may be approved to use propranolol if they could demonstrate their blood pressure was consistently stable.

Pilots intermittently using propranolol to treat symptoms such as performance anxiety are required to be assessed for other effects (such as low blood pressure and tiredness) and could be advised to not operate an aircraft within 24 hours of taking propranolol.

Additional medical considerations

The pilot had previously been diagnosed by their general practitioner as having a longstanding familial benign essential tremor, affecting their hand’s fine motor skills. To treat those symptoms, propranolol had been prescribed and was to be taken as needed. That tremor had also been noticed by many of the pilot’s flying friends and colleagues and was reported to be particularly evident when using hand tools such as screwdrivers, writing and pouring drinks. Flight examiners, instructors and passengers who had flown with the pilot advised that, although they were aware of the existence of the pilot’s tremor, they had not noticed it to affect the operation of the helicopter or aeroplanes being flown. 

The pilot completed an aviation medical with a CASA DAME every 2 years. That process required submission of an online applicant medical history questionnaire and then completion of a physical examination and tests with a DAME to assess the applicant’s ability to meet the relevant medical standard. This included assessing the applicant’s hand/eye coordination and checking for any symptoms or indications of neurological disease. 

The DAME had conducted the pilot’s last 3 medical renewals, with the last being conducted in January 2022, and did not recall the applicant having any tremor of clinical significance. Further, the pilot had not declared in their applicant medical history questionnaire they had symptoms or were receiving treatment of any movement disorder (including tremor), or that they had been prescribed any medications. Had a tremor of clinical significance been identified, the DAME reported that they would have referred the pilot to a neurologist for a specialist opinion. 

Extreme teeter and mast bumping 

Under certain specific flight conditions, semi-rigid rotor systems are susceptible to extreme teetering where the blades teeter beyond their normal operational range, resulting in what is commonly known as ‘mast bumping’. Mast bumping is the act of the inboard end of the blade (the spindle) or main rotor hub contacting the main rotor shaft. In R22 helicopters, this can generally be identified by extensive damage to the teeter stops and varying degrees of structural damage to, and possible fracture of, the mast. 

Once the teeter stops are damaged or fractured, both spindle tusks may also fracture. This allows the main rotor blades to flap even further resulting in excessive bending loads to the main rotor pitch change links and subsequent fracture of one or both links. Failure of a pitch link can result in the associated blade reacting to the aerodynamic and centripetal forces on the blade and rotating about its pitch axis, making the helicopter uncontrollable. 

As documented in many investigation reports worldwide, scenarios that have been linked to mast bumping include low-g and/or low rotor RPM/rotor stall, in conjunction with delayed and/or inappropriate flight control inputs.[32]

The low-g condition

‘G’ or ‘g’ is an abbreviation for the acceleration due to the earth’s gravity. Positive ‘g’ is necessary for helicopters to respond to pilot control inputs. In a low-g condition (that is, approaching the feeling of weightlessness),[33],[34] the pilot’s ability to control the attitude of the helicopter is greatly reduced. 

The United States Federal Aviation Administration (FAA) Helicopter Flying Handbook further described low-g effects, including:

Helicopters rely on positive G to provide much or all of their response to pilot control inputs. The pilot uses the cyclic to tilt the rotor disk, and, at one G, the rotor is producing thrust equal to aircraft weight. The tilting of the thrust vector provides a moment about the center of gravity to pitch or roll the fuselage. In a low-G condition, the thrust and consequently the control authority are greatly reduced.

Although their control ability is reduced, multi-bladed (three or more blades) helicopters can generate some moment about the fuselage independent of thrust due to the rotor hub design with the blade attachment offset from the center of rotation. However, helicopters with two-bladed teetering rotors rely entirely on the tilt of the thrust vector for control. Therefore, low-G conditions can be catastrophic for two-bladed helicopters.

… (when the helicopter) enters a low-G condition. Thrust is reduced, and the pilot has lost control of fuselage attitude but may not immediately realize it. Tail rotor thrust or other aerodynamic factors will often induce a roll. The pilot still has control of the rotor disk, and may instinctively try to correct the roll, but the fuselage does not respond due to the lack of thrust. If the fuselage is rolling right, and the pilot puts in left cyclic to correct, the combination of fuselage angle to the right and rotor disk angle to the left becomes quite large and may exceed the clearances built into the rotor hub. This results in the hub contacting the rotor mast, which is known as mast bumping.

RHC stated that extreme teetering and subsequent mast bumping can result from the pilot attempting to recover from an uncommanded right roll while in a low-g condition. Extensive investigation has shown that inappropriate recovery flight control inputs often resulted in the main rotor blade impacting the forward fuselage.

Low rotor RPM and stall

The R22 helicopter, with its low rotor system mass and relatively high RPM, is described as ‘low inertia’. In low inertia systems, rotor RPM is gained and lost very easily. Low rotor RPM occurs when the rotor can no longer produce enough lift to support the weight of the helicopter, and it will start to descend. If this situation is not quickly and effectively managed, the rotor RPM can reduce to a point where one, or both, main rotor blade/s stall. According to RHC safety notice[35] SN-24 Low RPM rotor stall can be fatal, rotor stall recovery is ‘virtually impossible’.

Low-rotor RPM can occur at almost any time, during power-on and power-off operations and is usually the result of improperly coordinating the collective and throttle, including overpitching or a failure to quickly lower the collective in an emergency such as engine failure or power reduction.

RHC safety notice SN-10 Fatal accidents caused by low rotor RPM rotor stall included:

A primary cause of fatal accidents in light helicopters is failure to maintain rotor RPM. To avoid this, every pilot must have his reflexes conditioned so he will instantly add throttle and lower collective to maintain RPM in any emergency. 

…

Power available from the engine is directly proportional to RPM. If the RPM drops 10%, there is 10% less power. With less power, the helicopter will start to settle, and if the collective is raised to stop it from settling, the RPM will be pulled down even lower, causing the ship to settle even faster. If the pilot not only fails to lower collective, but instead pulls up on the collective to keep the ship from going down, the rotor will stall almost immediately. When it stalls, the blades will either "blow back" and cut off the tailcone or it will just stop flying, allowing the helicopter to fall at an extreme rate. In either case, the resulting crash is likely to be fatal.

No matter what causes the low rotor RPM, the pilot must first roll on throttle and lower the collective simultaneously to recover RPM before investigating the problem. It must be a conditioned reflex. In forward flight, applying aft cyclic to bleed off airspeed will also help recover lost RPM.

The low rotor RPM warning lamp and horn will activate when the rotor RPM reduces to 97% or below. The warning lamp is located on the top of the instrument panel and the horn can be heard in the cabin and in both headsets. The POH stated that ‘catastrophic rotor stall could occur if the rotor RPM ever drops below 80% plus 1% per 1,000 ft of altitude’. Further, the FAA Helicopter Flying Handbook stated that ‘low inertia rotor systems can become unrecoverable in 2 seconds or less if the RPM is not regained immediately’.

Potential factors leading to low-g and/or low rotor RPM/rotor stall

As a possible explanation for delayed or inappropriate control inputs that may have preceded a low-g condition or low rotor RPM and stall, the investigation explored the following scenarios:

Low-g pushover 

RHC safety notice SN-11 Low-g pushovers – extremely dangerous stated ‘pushing the cyclic forward following a pull-up or rapid climb, or even from level flight, produces a low-g (weightless) condition’. It also stated that severe in-flight mast bumping usually results in main rotor shaft separation and/or rotor blade contact with the fuselage. The following warning was included:

Never attempt to demonstrate or experiment with low-G manoeuvres, regardless of your skill or experience level. Even highly experienced test pilots have been killed investigating the low-G flight condition. Always use great care to avoid any manoeuvre which could result in a low-G condition. Low-G mast bumping accidents are almost always fatal.

The ATSB spoke with the pilot’s regular helicopter flight instructor and other pilots who routinely flew with the pilot in VH-RAS. They all reported that the pilot demonstrated awareness of low-g flight conditions and the danger in entering a pushover manoeuvre, whether deliberate or unintentional. It was therefore determined to be unlikely that the pilot initiated a deliberate low-g pushover.

Turbulence

The FAA Helicopter Flying Handbook stated that ‘turbulence, especially severe downdrafts, can also cause a low-g condition and, when combined with high airspeed, may lead to mast bumping’. RHC safety notice SN-32 referred to flying in high winds or turbulence,[36] firstly stating that it should be avoided. It continued, noting that ‘a pilot’s improper application of control inputs in response to turbulence can increase the likelihood of a mast bumping accident’. In addition, in March 2024, the ATSB published the safety advisory notice Anticipate turbulence and slow down, which included:

Awareness of conditions likely to produce turbulence, and slowing down prior to encountering turbulence, could increase the time available to recognise and respond to a low-g condition in Robinson Helicopters.

Several pilots who departed Koorda that morning reported encountering some turbulence over the Cowcowing Lakes area.[37] RHC recommended a reduction in airspeed when encountering turbulence. The recorded data for VH-RAS did not indicate any significant deviation to altitude or airspeed typically seen in moderate, severe or extreme turbulence. In addition, the data did not indicate any significant reduction in airspeed in the last minutes of the flight, as recommended by RHC when encountering significant turbulence.[38],[39] 

RHC also advised helicopters that are lightly loaded may be more susceptible to turbulence than heavy helicopters. As the weight of VH-RAS was calculated to be at, or just above, its maximum weight at the time of the accident, this potentially reduced any effects of turbulence that may have been encountered.

Overpitching

As the collective is raised, there is a simultaneous and equal increase in pitch angle of both main rotor blades. An increase in pitch angle also results in increased drag on the main rotor blades. To counter this adverse effect, the R22 has a throttle correlator mechanism attached to the collective control that increases the engine’s throttle when the collective is raised.

Overpitching is a condition that happens when the collective pitch is increased to a point where the angle of attack of the main rotor blades creates extra drag and maximum engine power cannot maintain or restore normal operation rotor RPM. One typical scenario often occurs during take-off, where the pilot raises the collective lever to a point beyond the full throttle position (where full throttle was required to maintain RPM), then there will be more power required by the rotors than power available from the engine, resulting in a rotor RPM decay. However, as the helicopter had departed Koorda without incident, this was considered unlikely for this occurrence.

Overpitching can also occur if the pilot raises the collective lever at a rate that is faster than the correlator will open the throttle (to avoid a bird for example), while not compensating for the increased drag by manually increasing the throttle. In this case, the rotor RPM may rapidly decay to a level that is too low for the engine power available to recover.

In addition, overpitching is more likely to occur at a high weight and/or high altitude, where the rotor blades are already operating at larger pitch angles.

Any application of collective to arrest the descent further increases rotor drag and reduces rotor RPM. The situation can rapidly deteriorate resulting in the rotor blades effectively stalling and significantly reduced lift. 

Potential for negative transfer of learning in an emergency situation

The pilot had considerable aeroplane operational experience, including flight activity endorsements to conduct aerobatics, spinning and formation flying. The investigation considered if the pilot may have reacted to an unexpected situation with an inadvertent ‘aeroplane’ control input, as described in SN-29 Airline pilots high risk when flying helicopters, which could have induced a low-g scenario. Specifically, the notice stated that:

…The airplane pilot may fly the helicopter well when doing normal maneuvers under ordinary conditions when there is time to think about the proper control response. But when required to react suddenly under unexpected circumstances, he may revert to his airplane reactions and commit a fatal error. Under those conditions, his hands and feet move purely by reaction without conscious thought. Those reactions may well be based on his greater experience, ie., the reactions developed flying airplanes.

Records indicated the majority of the pilot’s recent flying had been conducted in VH-RAS.[40] In addition, people who had flown in VH-RAS reported the pilot to being cognisant of the dangers of inappropriate control inputs when operating an R22 helicopter. Therefore, while a scenario where the pilot inadvertently used aeroplane flight control actions was considered a possibility, it was assessed to be unlikely in this occurrence given the pilot’s helicopter experience.

Inadvertent or inappropriate dual control input 

Several sources reported that, on occasion, the pilot had offered passengers with flying experience the opportunity to ‘fly’ the helicopter using the left seat dual flight controls. Some passengers reported that they had flown the helicopter using the cyclic control, while the pilot retained control of the collective. One of those passengers had remarked that the pilot had been closely supervising them and had cautioned them about making abrupt forward control inputs. Another passenger recalled that they had been offered but decided to decline the opportunity to fly the helicopter. In this case, the pilot had emphasised the sensitivity of the flight controls and highlighted the hazards with making abrupt control inputs. 

RHC safety notice SN-20 Beware of demonstration or initial training flights noted that, ‘a disproportionate number of fatal and non-fatal accidents occur during demonstration or initial training flights’. Further, if a ‘student’ was to make sudden large control movements in the wrong direction, an experienced instructor may not necessarily be able to recover control of the helicopter. The notice also highlighted the importance of thoroughly explaining to students the ‘extreme sensitivity of the controls in a light helicopter’. 

RHC safety notice SN-44 Carrying passengers also identified that carrying a passenger can potentially increase risk as they add workload and distraction. The notice specifically stated:

  • Always remove passenger-side controls. 
  • Caution passengers against inadvertently bumping the cyclic center post.

Another potential source of confusion for someone inexperienced in flying helicopters is the throttle operation. The throttle twist control, located on the end of each collective, is operated by rolling the hand away from the body (or outboard) to increase engine power, and rolling toward the body to decrease. This is opposite to throttle controls fitted to vehicles such as motorcycles and the steering arm on boat outboard motors.

Despite the above, without any onboard recording devices such as a cockpit camera, the ATSB was unable to determine if the passenger was in control or if they had inadvertently bumped or moved the controls. 

Other scenarios

The investigation considered other scenarios that may induce a large control input, such as avoiding a bird or a door opening or separating in-flight. Bird avoidance may have resulted in an abrupt control movement, however, nil evidence of a strike was found in and around the wreckage. Further, one of the pilots in the group and a local resident stated that they did not observe any bird activity in the area. 

If a door had opened, this had potential to temporarily distract the pilot and/or the passenger, or result in an inadvertent control input while trying to close the door. [41] Noting that the left door could not be identified at the accident site, operating the helicopter with one or both doors removed is permitted, with the manufacturer advising to calculate weight and balance as required[42] and ensure loose articles are secured in the cabin. Liberation of the left door had the potential to strike the tail cone or tail rotor assembly, however, there was no evidence of the door coming into contact with any portion of the tailcone.

While these scenarios remained a possibility, there was insufficient evidence to conclude probability.

Engine power loss scenarios 

While the governor switch was found in the OFF selection, the position prior to impact could not be determined and post-accident functionality testing could not be performed due to the damage sustained. However, it remained a possibility for an intermittent issue (for example a cylinder misfire, fouled spark plug or sticky valve), to briefly affect engine operation, which did not result in any visible damage. An intermittent loss of engine power will typically result in a ‘kick’ (nose left yaw). It was possible that a sudden yaw may have contributed to either the pilot or passenger making a large control input, but there was insufficient evidence to conclude probability.

There have also been cases where an engine stoppage was inadvertently induced by rolling off the throttle too fast or the mixture control being pulled instead of the carburettor heat or another control.[43] 

Acknowledging the limitations of the Civil Aviation Safety Authority Carburettor icing probability chart and variations to induction systems depending on engine installation, the investigation also considered the possibility of carburettor icing. Carburettor ice is formed when the normal process of vaporising fuel in a carburettor cools the carburettor throat so much that ice forms from the moisture in the airflow, which can restrict airflow to the engine. This is more likely to occur at low engine power settings due to the added cooling effect of the partially-closed throttle butterfly.[44],[45] This valve provides more area on which the ice can accrete and increases the partial vacuum downstream of the valve. This causes further chilling of the air and the water droplets, further increasing the likelihood of ice accretion. The effect of carburettor icing includes reduced power output, rough running and in some cases engine failure. Further, the risk of ice build-up in the carburettor can be high even with no visible moisture and at temperatures of up to 38 °C. 

The RHC safety notice SN-25 Carburetor Ice also stated that, ‘avoidable accidents have been attributed to engine stoppage due to carburetor ice. When used properly, the carburetor heat and carb heat assist systems on the R22 and R44 will prevent carburetor ice’. The European Union Aviation Safety Agency safety information bulletin No: 2010-03 Carburetor Icing Prevention, also noted that:

In a helicopter, icing can develop quite insidiously and the effect on the engine is less obvious. Furthermore, should the engine stop, an immediate entry to autorotation is necessary to prevent catastrophic reduction of rotor RPM, and the descent rate, usually around 2 000 feet per minute, is such that there is rarely time to attempt a restart. 

RHC safety notice SN-31 Governor can mask carb ice stated that, when ice begins to form in the carburettor, a properly functioning governor will increase throttle to maintain engine RPM, which will also result in constant manifold pressure. Once the governor has opened the throttle completely it can no longer maintain rotor RPM and the engine RPM will reduce, which may be the first point a pilot is aware of the icing, if they had not been monitoring the manifold pressure and carburettor air temperature gauges.[46],[47] Further, application of heat at this late stage will melt any ice, which could result in engine stoppage.

The environmental conditions and time between the accident and the ATSB’s examination of the wreckage meant that any icing in the throat of the carburettor would have melted and not been detectable. Also, the examination could not determine if carburettor heat was in use prior to impact nor were there any reliable needle impact marks identified on the carburettor air temperature gauge. Therefore, while local conditions were conducive to the possibility of the formation of carburettor ice, it was not possible to establish if VH-RAS was affected by carburettor icing at any stage of the flight.

Overall, the ATSB’s examination of the engine did not identify any issue that may have affected operation and noting that the engine was likely rotating at impact, may suggest that an engine stoppage had not occurred. However, the investigation could not conclude an intermittent engine issue and/or that carburettor icing occurred, resulting in a reduction in power and the requirement to enter autorotation. Equally, the inverted portion of the descent had the potential to interrupt fuel flow to the engine via the gravity‑fed fuel system and reduce engine power.

In the event of an engine power failure above 500 ft above ground level, the emergency procedures section of the POH stated to:

  • Lower collective immediately to maintain rotor RPM
  • Establish a steady glide at approximately 65 KIAS (knots indicated airspeed)
  • Adjust collective to keep RPM between 97 and 100% or apply full collective down if light weight prevents attaining above 97%.

Airspeed and descent rates may be variable during controlled descent. Descent rates during autorotation vary depending on helicopter configuration and local conditions, however, anywhere between 1,400 to 1,900 ft/min can be expected.[48]

However, using the recorded data, the investigation estimated that the helicopter collided with terrain between 10 to 15 seconds after departing from controlled flight. The descent rate of about 9,000 ft/min during this period was inconsistent with the helicopter being established in an autorotative descent. 

Low-g or low rotor RPM signatures

The ATSB liaised with RHC and reviewed investigation reports from the United Kingdom, United States, Europe, and New Zealand. Excessive teeter and mast bumping, such as fractured tusks and teeter stops, were associated with a combination of these scenarios. 

A sudden roll to the right is often associated with a low-g event. Typical low-g wreckage signatures include a main rotor blade strike to the cabin/forward fuselage (where the blade/s cuts through the helicopter at high velocity) and mast separation (often at the mast bump/teeter stop location). In addition, a long/large debris trail is indicative of in‑flight break‑up initiating when the helicopter was within normal operating parameters.

Low rotor RPM and rotor stall signatures identified in many investigation reports included a rotor strike to the tailcone, main rotor blade coning,[49] spindle impact marks on the main rotor head, little to no rotational ground marks, and the helicopter nosing over and a vertical descent with a small debris field. However, it has been documented that, since RHC changed the main rotor blade construction from stainless steel skin to aluminium skin, damage to blade skins due to extreme coning as a result of low rotor RPM is now less than previously observed.[50]

A rotor strike to a solid object, such as the fuselage, a tree, or the ground, can stop a low powered engine. This is in contrast to where rotor blades often fracture into multiple small pieces during a rotor strike with full engine power. 

Similar occurrences

A review of investigation reports from Australia, New Zealand, United Kingdom, United Sates, South Africa, and Europe identified at least 3 reports that had signatures very similar to this occurrence. These are summarised below.

German Federal Bureau of Aircraft Accident Investigation BFU21-0949-3X  

On 17 October 2021, recorded data from a Robinson R44 Raven II showed that, while in cruise about 1,900 ft above mean sea level, the helicopter abruptly climbed about 200 ft, followed almost immediately by a rapid descent. Coincident to this, the recorded ground speed rapidly decayed from about 100 kt to zero. The pilot and 2 passengers were fatally injured.

The mast had fractured below the swashplate and the rotor head, with the blades attached, came to rest on top of the upright destroyed fuselage. Typical mast bump and in‑flight break‑up signatures were found on the mast and rotor head. One main rotor blade showed damage consistent with it striking the forward fuselage. In addition, the left seat (passenger) dual flight controls were installed.

The investigation concluded the helicopter likely entered a low-g condition that led to mast bumping ‘due to erroneous control inputs, which resulted in the rotor hitting the fuselage and in‑flight break-up’. Of note, the Bureau indicated that it was quite possible that the passenger was allowed to control the helicopter during the flight and unknowingly initiated a pull‑up or push over. However, it could not be established with any certainty who was in control of the helicopter at the time of the occurrence.

ATSB investigation AO-2020-061

On the afternoon of 2 December 2020, a RHC R44 Raven I, registered VH-HGU, departed Goulburn Airport, New South Wales with a student pilot and instructor on board. The helicopter flew east, and the last recorded automatic dependent surveillance broadcast detected it descending into a valley in the Bungonia State Conservation Area. A search commenced when the helicopter did not return as expected, and the wreckage of VH-HGU was found in a valley, approximately 4 km north-west of its last ADS-B transmission. Both pilots were fatally injured, and the helicopter was destroyed.

Although fire and impact damage had destroyed some parts of the helicopter, the evidence available gave no indication that the helicopter was operating abnormally prior to an in‑flight break-up. Components recovered near the beginning of the 275 m wreckage trail indicated that a main rotor blade had struck the left side of the fuselage at the beginning of the break‑up sequence. No evidence was found to indicate pre-existing mechanical defects or issues that could have prevented normal engine operation. While a transient condition such as a partial or complete power loss could not be ruled out, such an event should not have resulted in an in-flight break-up.

The investigation concluded that, while flying in the vicinity of the valley, the helicopter entered a low-g condition due to turbulence, inappropriate control inputs, or a combination of both. This condition, probably in combination with inappropriate recovery control inputs resulted in extreme teetering of the main rotor. A mast bump occurred as a result, and the helicopter subsequently broke up in-flight.

United Kingdom Air Accidents Investigation Branch G‑CHZN

On 6 January 2012, after about 1 hr and 28 minutes into a private flight, and when about 1,440 ft above the ground, the Robinson R22 disappeared from air traffic control radar. Witnesses reported hearing a pop sound and some described the helicopter rolling to the left, with one person saying the helicopter pitched up prior to the left roll. The helicopter then fell, inverted, to the ground. The pilot, the only person on board, sustained fatal injuries.

Both main rotor blades had separated from the hub. There was evidence of rotor blade strike to the forward left fuselage. The tailcone remained attached to the fuselage and there was no evidence of rotor strike. An engine examination did not identify any issue or failure that would prevent it from operating normally. The local conditions at the time were calculated to be conducive to moderate or serious carburettor icing at any engine power.

The investigation explored low-g and low rotor RPM, with the wreckage exhibiting signatures from both scenarios. Pilot incapacitation, carburettor icing and avoiding a bird were also considered as possible contributing events. The report concluded that the mast bumping ‘was probably caused by a loss of rotor RPM (not followed by rapid lowering of the collective), a low-g pushover, a large abrupt control input – or a combination thereof’. Further, it was noted that low-g or a large abrupt control input ‘could have been generated for a number of reasons, and the light control forces in the R22 make it relatively easy to enter such conditions’.

Safety analysis

Introduction

On the morning of 2 October 2022, a Robinson Helicopter R22 Beta II, registered VH‑RAS, departed Koorda, Western Australia, on a return flight to Jandakot via Northam aerodrome. Shortly after reaching cruise, the helicopter departed from controlled flight, descended rapidly, and collided with terrain inverted. The 2 occupants were fatally injured, and the helicopter was destroyed.

This analysis will examine the factors that likely contributed to the in-flight break-up, which include entering a low-g and/or low rotor RPM/rotor stall condition. It will also discuss the fitment of dual flight controls when carrying passengers and the importance of disclosing to aviation medical specialists the use of prescription medication for a medical condition. 

Departure from controlled flight due to in-flight break-up

Analysis of the recorded data indicated that the helicopter took off from Koorda and climbed to a cruise altitude with no apparent issues. However, shortly after, the data broadcast by the iPhone was consistent with the helicopter departing controlled flight. The groundspeed quickly reduced and the helicopter rapidly descended at a rate significantly in excess of what would be expected if an autorotation was being conducted by the pilot. The trajectory apparent in the analysis of the iPhone data closely correlated with the location of the helicopter wreckage.

Extreme teetering

The site and wreckage examination identified signatures consistent with the main rotor assembly being subject to excessive teeter and mast bumping. This included fracture of the spindle tusks, teeter stops, pitch links, and main rotor strike to the fuselage. While the main rotor assembly separation location was lower than the typical mast bumping, impact damage in the vicinity of the teeter stops was indicative of the severe forces associated with extreme teetering. In this instance, the mast fracture was likely associated with pitch horn impact, from a freely rotating blade, and determined to have occurred later in the accident sequence. As a result of the extreme teetering and mast bumping, the helicopter was subject to structural failure and in-flight break-up, beyond which sustained flight was no longer possible.   

Low-g and/or low rotor RPM/stall conditions

The ATSB examined several previous accidents with similar circumstances, all of which identified low-g or low rotor RPM/rotor stall as conditions that could lead to extreme teetering and/or mast bumping and an in-flight break-up.

Examination of the dual tachometer identified signatures of low rotor and engine RPM at impact, however, this may not be indicative of operational conditions just prior to the departure from controlled flight. Although the small debris field and flight data showing an almost vertical descent were representative of low rotor RPM/rotor stall, there was only minor coning to the main rotor blades, but this may have been due to the aluminium skin construction of the main rotor blades. In addition, it was unknown if the low rotor RPM warning light was illuminated as the lamp was destroyed.

While the helicopter impacted the ground inverted, it could not be established if this was initiated by a right roll (low-g) or a nose over event (low rotor RPM). The method of the main rotor blade strike to the cabin was consistent with a mast bumping event and likely occurred during the later stage of the uncontrolled descent.

Multiple scenarios were determined to have preceded a low‑g or low rotor RPM condition, which were also explored by the ATSB. These included responding to an engine power loss/failure (such as from carburettor icing or governor unit malfunction), turbulence, low-g pushover, overpitching, a medical event, birdstrike or bird avoidance, a door opening or separating in-flight, or other large control input for undetermined reasons. While some of these were considered unlikely, as discussed previously, some were inconclusive due to insufficient evidence and the absence of an onboard camera. 

However, the preceding factors examined result from, or could be exacerbated by, pilot flight control inputs. For example, inappropriate inputs may result in a low-g pushover or overpitching, incorrect recovery inputs when responding to turbulence may result in low-g, or delayed inputs when responding to a low rotor RPM may lead to rotor stall. In this instance, the ATSB was unable to establish which scenario preceded the other during the accident sequence, in that, pilot reaction to low-g may have inadvertently induced a low rotor RPM state, or vice versa.

Research has shown that, even if a helicopter enters a low-g or low rotor RPM condition it is recoverable through prompt and appropriate control inputs. The RHC POH and safety notices provide detailed information on how to avoid these conditions, and best practice for recovering control if required. It is important to acknowledge that the automation of some systems (for example, the carburettor heat assist and engine RPM governor) may mask a developing malfunction or adverse condition. While flight training assists in appropriate recovery techniques becoming instinctual, the pilot must remain vigilant throughout the entire flight to avoid a delayed reaction in an unexpected situation. This is critical as the R22 low inertia rotor system means a pilot could have less than 2 seconds to identify the situation and react appropriately before it becomes unrecoverable.

In summary, the site and wreckage examination identified signatures that were likely indicative of a low-g and/or low rotor RPM/rotor stall condition. While an onboard camera was not fitted, given the nature of the events that typically precede these conditions, it was also likely that delayed and/or inappropriate flight control inputs were a factor, although the exact circumstances could not be conclusively determined. However, it is known that low‑g and low rotor RPM/rotor stall conditions can be catastrophic for helicopters with semi-rigid rotor heads. Therefore, a pilot’s ability to identify the condition and promptly apply the correct flight control inputs is vital to effective recovery and continued safe operation.  

Dual flight controls

Examination of the wreckage identified that the quick-disconnect dual flight controls were installed at the left seat (passenger) location. It was also established that, on occasion, the pilot allowed passengers with previous flying experience to operate the cyclic control. As large, abrupt control inputs are one precursor to teetering/mast bumping events, the ATSB considered the possibility of an inadvertent control input from the passenger, such as bumping the controls, or the passenger having control of the cyclic and/or any of the other dual controls. 

The cyclic T-bar ‘see-saw’ design meant that, if the person seated in the left seat has control of the helicopter, the cyclic grip of the right seat person would be in a higher-than-normal operating position. In a situation where a passenger has made an inappropriate control input from the left seat, the positioning of the T-bar could potentially delay the pilot from regaining control. RHC noted that, even within a structured flying training context, the instructor may not be able to regain control of the helicopter in time to prevent a loss of control.

Having dual flight controls installed increases the risk of inadvertent control inputs by a passenger. This is supported by the advice in the R22 POH to remove the controls and in a further safety notice from RHC, which described the risks when carrying passengers. While there was insufficient evidence in this case to determine if the passenger made an inadvertent control input or if they were operating any of the controls during the flight, either action had the potential to contribute to the helicopter entering a low-g and/or low rotor RPM condition. 

In addition, to avoid an inappropriate input as much as possible, unless operating in a flight training environment with a qualified instructor, under no circumstances should an unqualified person be permitted to manipulate the helicopter’s controls. As emphasised in the RHC safety notice on demonstration or initial training flights, this is particularly relevant in the R22 type helicopter, where the low inertia rotor system affords a pilot very little time to react appropriately and regain control.

Disclosure of medical information

While a medical event prior to the in-flight break-up could not be determined in the absence of an onboard camera, the investigation established that the pilot had been prescribed and was taking medication (propranolol) to treat symptoms of their hand tremor. However, this information had not been declared to the DAME during their recent medical examinations. This precluded an opportunity by CASA and/or the DAME to complete a formal assessment of that condition and the use of medication for aeromedical significance and fully assess the pilot’s ability to meet the relevant medical standard. 

Based on information provided to the ATSB by CASA and the DAME who had completed the pilot’s most recent medical renewals, neither the hand tremor nor the prescription medication used to treat those symptoms would necessarily have precluded the pilot being issued an aviation medical certificate. 

Although the source of the quinine or quinidine could not be determined, the level of this and the propranolol detected were unlikely to have affected the pilot’s ability to operate the helicopter, as assessed by the consultant pharmacologist. Similarly, those who had flown with the pilot stated that they did not recall the tremor affecting their ability to fly. 

Nevertheless, it is important to declare all medications and medical conditions to address risks that could affect performance. While it is acknowledged that some pilots may have concerns about not meeting medical certificate requirements if they make such declarations, pathways exist for managing certain medical conditions while maintaining a medical certificate.

Cockpit cameras

The ATSB explored multiple scenarios that were considered to contribute to extreme teetering and mast bumping accidents. However, there was insufficient evidence available to determine the events immediately prior to the in-flight break-up. As noted by the Transport Accident Investigation Commission (2021), a significant proportion of mast bumping accidents in New Zealand have occurred in low-g flight conditions. However, ‘Part of the problem is that the available evidence has not allowed the circumstances and causes of all of these ‘mast bumping’ accidents to be fully determined’. As such, the Commission recommended the need for cockpit video recorders and/or other means to capture data in certain classes of helicopter. 

In recent years, RHC has introduced cockpit cameras into the R66 and R44 helicopters as standard. The inclusion of these cameras will provide vital footage and audio information to investigators and manufacturers. Understanding the circumstances leading up to extreme teeter and in-flight break events, will assist in determining appropriate steps for ongoing safety improvement. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the in-flight break-up involving Robinson R22 Beta II, VH-RAS, 13 km south-west of Koorda, Western Australia, on 2 October 2022.

Contributing factors

  • Shortly after reaching cruise altitude, for reasons that could not be determined, it was likely that the helicopter entered a low-g and/or low rotor RPM/rotor stall condition. This, along with delayed or inappropriate control inputs, or a combination of both, resulted in extreme teetering of the main rotor assembly and subsequent in‑flight break-up.

Other factors that increased risk

  • Quick-disconnect dual flight controls were installed in a position occupied by a passenger, which increased the risk of inadvertent or inappropriate passenger control input.
  • The pilot did not disclose their use of a prescription medication being used to treat symptoms of a medical condition to the Civil Aviation Safety Authority. This precluded specialist consideration and management of the on-going flight safety risk the medical condition and medication may have posed.

Other findings

  • In helicopters with semi-rigid rotor heads, the circumstances leading to an in-flight break-up as a result of mast bumping and extreme teetering are not well documented. Recorded cockpit imagery would provide valuable information and insight into the events leading up to this type of occurrence.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • Civil Aviation Safety Authority 
  • Western Australia Police Force and the Coroner’s Court of Western Australia
  • Robinson Helicopter Company 
  • maintenance organisation for VH-RAS
  • Bureau of Meteorology
  • participants of the flying event
  • pilot’s flight instructor
  • people who had regularly flown with the pilot
  • consultant pharmacologist
  • recorded data from a handheld GPS receiver and OzRunways computer server.

References

Cullen, S.A. (2004). Mechanisms of injury in aircraft accidents. In Pathological aspects and associated biodynamics in aircraft accident investigation. Lecture series conducted at RTO HFM, Germany.

Gradwell, D. & Rainford, D.J. (Eds.) (2016). Ernsting’s Aviation and Space Medicine (5th ed). Boca Raton, FL: CRC Press.

Mornington-Sanford, R. (2014). It’s all in your head. Retrieved from https://www.morningtonsanfordaviation.com/

Mornington-Sanford, R. (2012). No ice, thank you. Retrieved from https://www.morningtonsanfordaviation.com/

Rivera, J., Talone, A.B., Boesser, C.T., Jentsch, F. & Yeh, M. (2014). Startle and surprise on the flight deck: Similarities, differences, and prevalence. In Proceedings of the human factors and ergonomics society annual meeting September 2014 (Vol. 58, No. 1, pp. 1047-1051). Sage CA: Los Angeles, CA: SAGE Publications.

Transport Accident Investigation Commission. (2021). Robinson helicopters: mast bumping accidents in NZ. Retrieved from https://www.taic.org.nz/watchlist/robinson-helicopters-mast-bumping-accidents-nz 

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • the maintenance organisation for VH-RAS
  • Civil Aviation Safety Authority
  • United States National Transportation Safety Board 
  • Robinson Helicopter Company
  • Bureau of Meteorology.

Submissions were received from the Robinson Helicopter Company. The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Appendices

Appendix A: Handheld GPS and iPhone data during accident flight
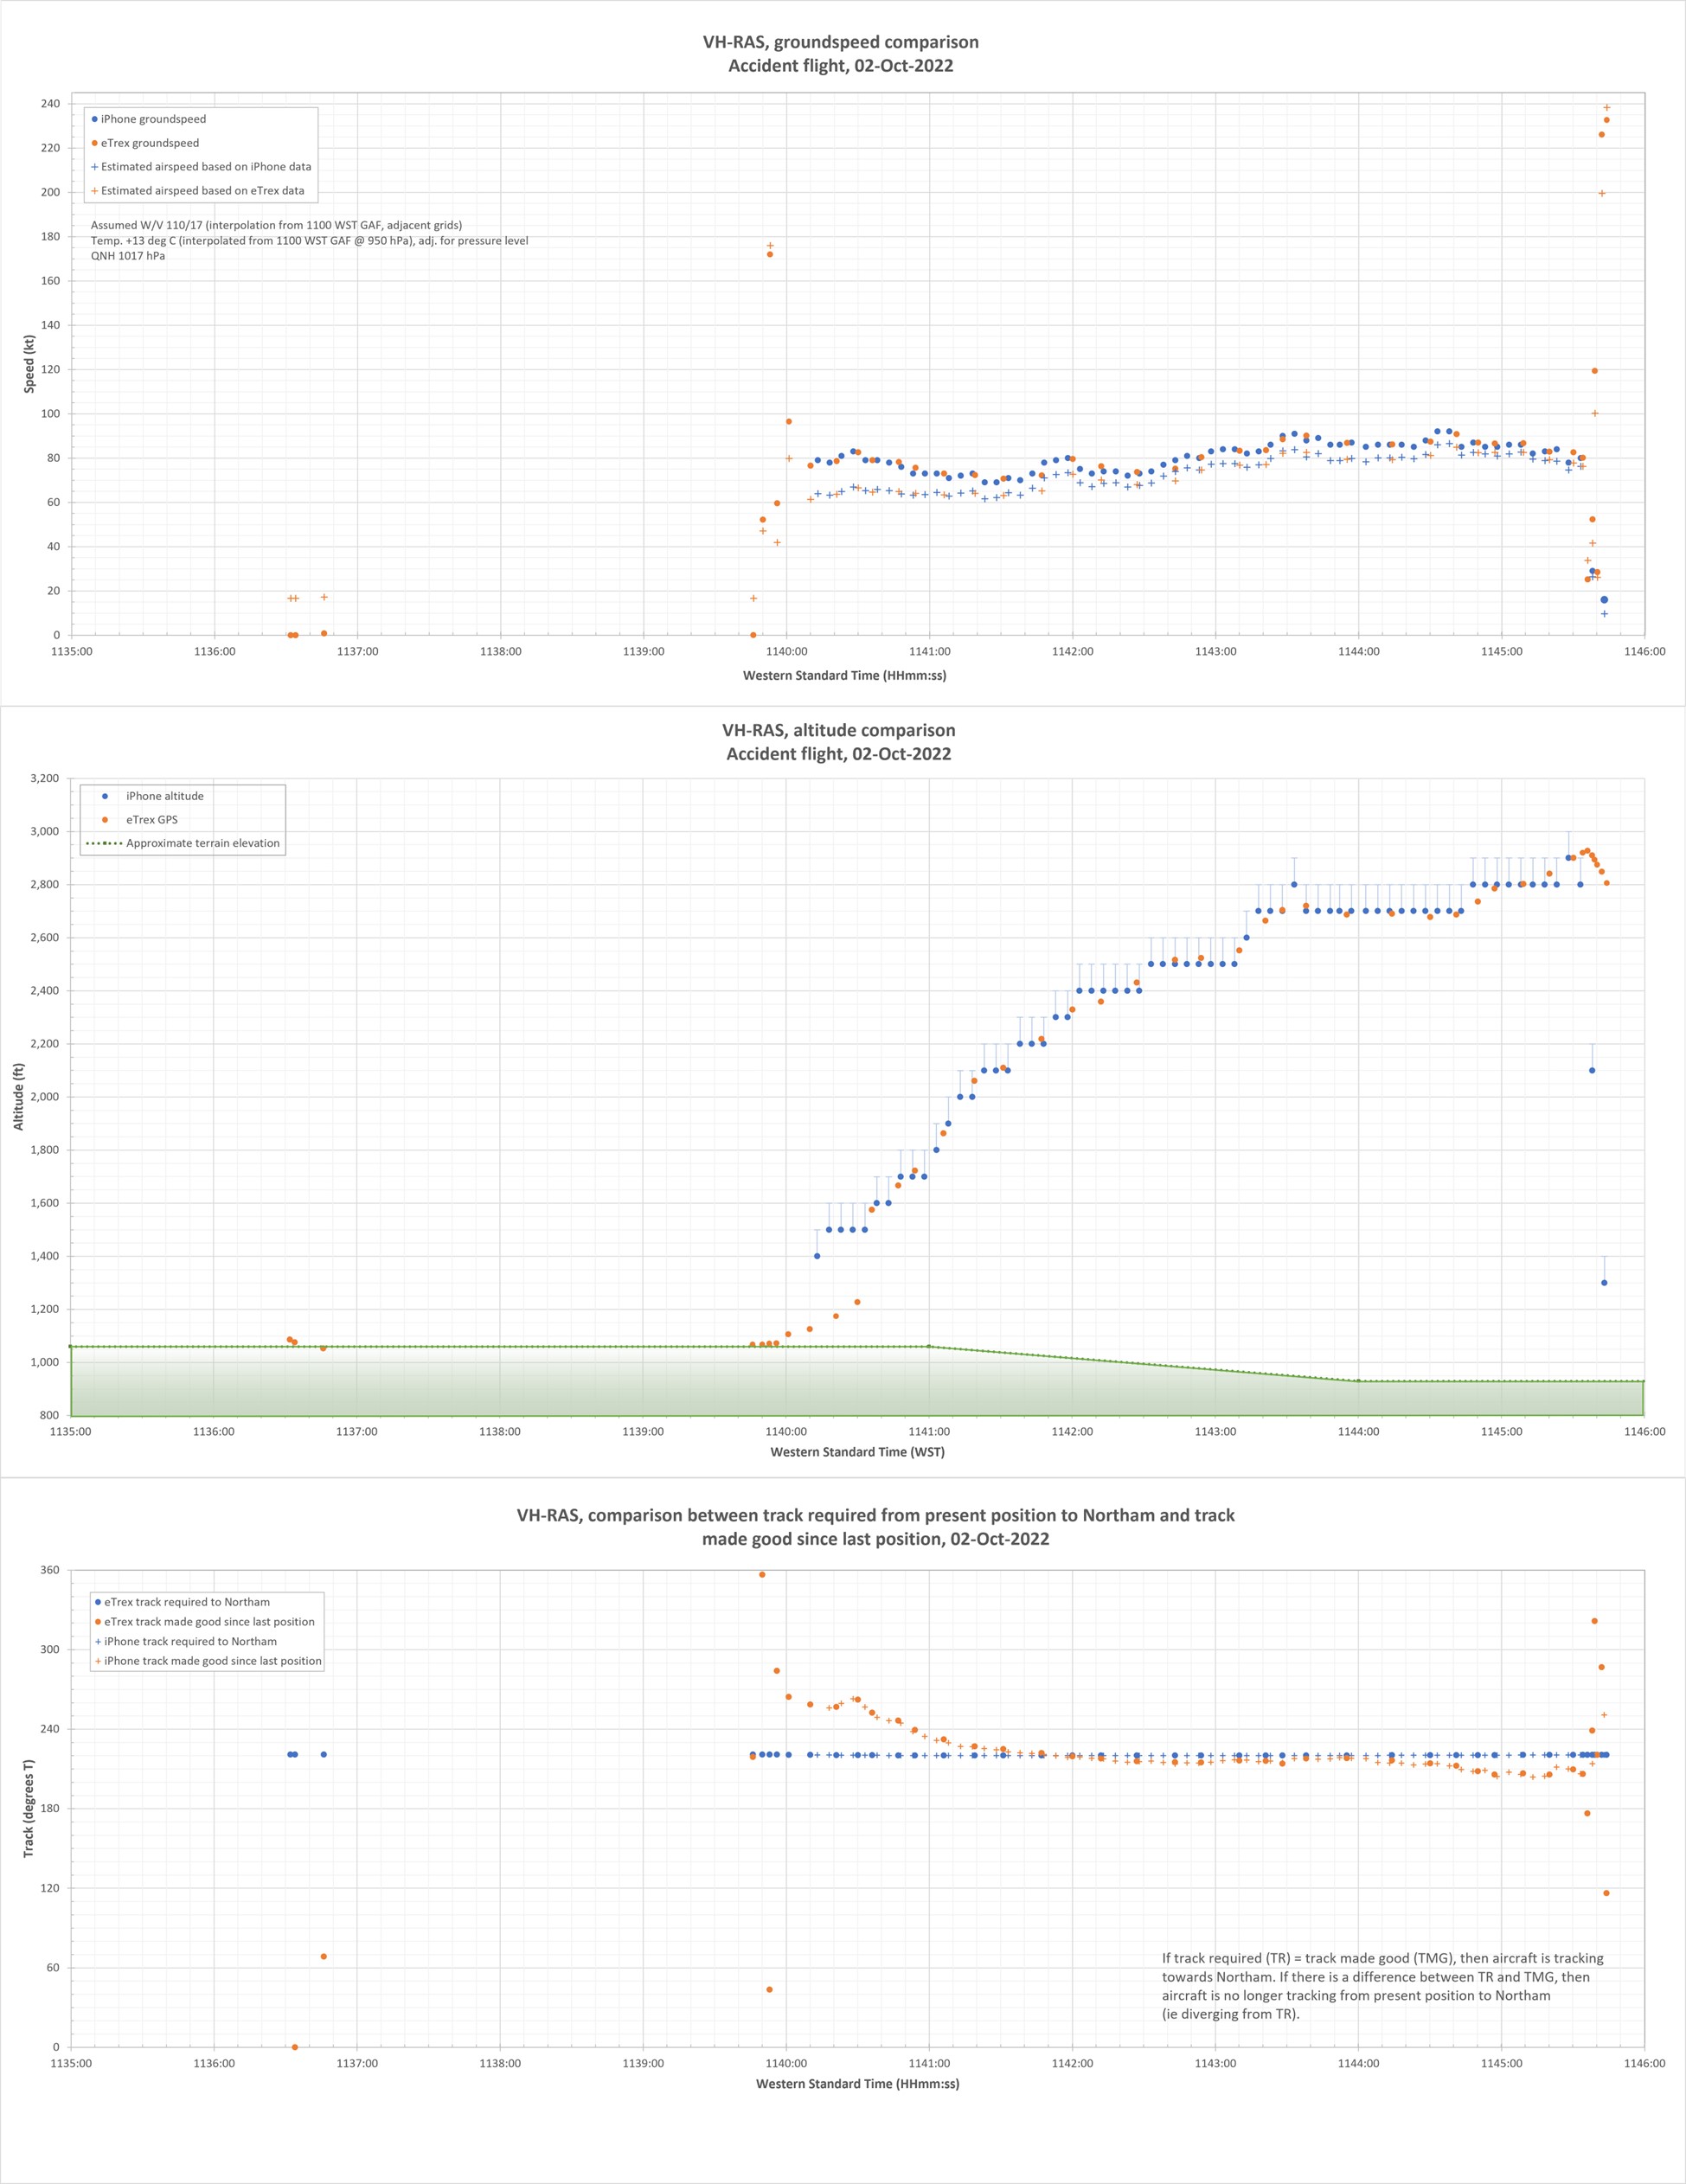
Appendix A: Handheld GPS and iPhone data during accident flight

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2024

CC BY logo

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to allow the pilot to see where the aircraft is going.

[2]     Avgas: a type of aviation fuel used in aircraft with a spark-ignited internal combustion engine.

[3]     Time-in-service recorded on the maintenance release was collective activated. Therefore, engine running time (warm up, cool down and any time with the helicopter running on the ground) was not included.

[4]     VH-RAS was the second R22 helicopter that the pilot had owned. Ownership of these helicopters was reported to have been transferred in 2016, as an operational consideration. Although VH-RAS had accumulated a higher number of hours total time in service prior to the ownership transfer, it had adequate hours available for the pilot’s purposes and their pattern of personal use.

[5]     The 45 minutes included engine running time while the helicopter was on the ground, which resulted in about 20 minutes recorded on the maintenance release.

[6]     Autorotation is a condition of descending flight where, following engine failure or deliberate disengagement, the rotor blades are driven solely by aerodynamic forces resulting from rate of descent airflow through the rotor. The rate of descent is determined mainly by airspeed.

[7]     Coning of main rotor blades: the upwards movement of the main rotor blades while they are rotating. This is usually in response to an increase in aerodynamic force as a result of a control input from the pilot. It is more pronounced at high weights and/or low main rotor speed.

[8]     The swashplate consists of 2 main parts: a stationary swashplate and a rotating swashplate. The stationary (inner) swashplate is mounted on the main rotor mast and is connected to the cyclic and collective controls by the push-pull tubes. It is able to tilt in all directions and move vertically. The rotating (outer) swashplate is mounted to the stationary swashplate by means of a bearing, which allows it to rotate with the mast. The swashplates move as one unit. The rotating swashplate is connected to the main rotor blade pitch horns by the pitch links.

[9]     Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.

[10]    Quick-disconnect flight controls do not require use of tooling to fit and remove and can therefore be accomplished by the pilot, without the requirement for a licenced aircraft maintenance engineer.

[11]    The POH required the pilot to use carburettor heat as required to keep the needle on the carburettor air temperature gauge out of the yellow arc (-15 to 5°C). In addition, carburettor heat was to be used with power settings below 18” mercury, regardless of the indicated carburettor air temperature.

[12]    Visual meteorological conditions: an aviation flight category in which visual flight rules flight is permitted – that is, conditions in which pilots have sufficient visibility to fly the aircraft while maintaining visual separation from terrain and other aircraft.

[13]    SIGMET provides information on the occurrence or expected occurrence of enroute weather phenomena that are potentially hazardous to aircraft.

[14]    AIRMET provides information on deteriorating conditions, not already included in the relevant graphical area forecast.

[15]    Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘scattered’ indicates that cloud is covering between about 3/8 and half of the sky.

[16]    Dewpoint: the temperature at which water vapour in the air starts to condense as the air cools. It is used, among other things, to predict the probability of aircraft carburettor icing or the likelihood of fog.

[17]    Light turbulence results in momentary slight and erratic changes in attitude and/or altitude with little effect on loose objects. Moderate turbulence results in appreciable changes in attitude and/or altitude but the pilot remains in control at all times, Unsecured will objects move and there is an appreciable strain on seatbelts. Severe turbulence results in large abrupt changes in attitude and/or altitude and a momentary loss of control. Unsecured objects are tossed about and the occupants are violently forced against seatbelts (Bureau of Meteorology).

[18]    OzRunways is an electronic flight bag application, utilising approved data for electronic maps and charts, and can be used to assist with navigation.

[19]    The Australian Maritime Safety Authority’s Joint Rescue Coordination Centre had used this data during their initial response to the reports of the missing helicopter, which assisted with its prompt location.

[20]    Taking into account the recorded groundspeed, the forecast wind, atmospheric pressure and temperature were used to estimate the calibrated airspeed (CAS) of the helicopter during the climb.

[21]    The intended path of the aircraft over the ground, from the current position to reach the next waypoint or destination. 

[22]    The aircraft’s actual track over the ground.

[23]    ‘SCEET’ is a high-temperature, flexible type aircraft ducting, constructed of 2 plies of silicone rubber impregnated fiberglass, supported with wire between the plies.

[24]    The passenger on the flight from Jandakot to Koorda advised the ATSB that both doors were fitted for that flight. In addition, no one reported seeing either door being removed at Koorda.

[25]    Filament stretching can be indicative of a hot filament and therefore the light being illuminated at impact.

[26]    The alternator lamp will illuminate to indicate low voltage, typically alternator failure or when the engine was at or below idle speed of about 55% (1,512 rpm).

[27]    The clutch lamp illuminates to indicate actuator operation and belt tensioning, which can occur during flight as the drive belts warm and stretch. Clutch lamp illumination could have been a normal function, or from the actuator trying to keep the drive belts tensioned due to airframe distortion during the accident sequence.

[28]    A full post-mortem includes a full external and internal examination. While the extent of a limited post-mortem examination can vary, an external examination is performed (https://www.pathwest.health.wa.gov.au/).

[29]    Carbon monoxide is a colourless, odourless and tasteless poisonous gas. It is a byproduct of the incomplete combustion of carbon containing materials such as exhaust gases from aircraft engines. 

[30]    Alkaloids are nitrogenous organic compounds of plant origin that have pronounced physiological effects on humans.

[31]    Load factor being experienced by the pilot/aircraft, in relation to the normal force of gravity.

[32]    Although not directly related to this occurrence, RHC has developed a symmetrical horizontal stabilizer for the R22 model helicopters, which enhances roll stability during high-speed flight. It is expected to be in production by mid-2024 with a retrofit kit for existing helicopters available shortly after. This new design is currently available on the R44 and R66 models.

[33]    All 2-bladed teetering main rotor systems helicopters, including Bell 205/UH-1 and Bell 206/L, are subject to mast bumping.

[34]    More detailed information is available from the Robinson Helicopter Company Low-G Mast Bumping Research paper, published 26 October 2022. Additional mast bumping research is available via Robinson Reference Materials - Robinson Helicopter Company

[35]    RHC safety notices mentioned in this report are included in the POH and also freely available via the website - https://robinsonheli.com/

[36]    Atmospheric turbulent eddies occur in a range of scales from hundreds of kilometres down to centimetres. Aircraft bumpiness is most pronounced when eddies are about the size of the aircraft, i.e. in the order of one hundred metres or so for commercial aircraft, to tens of metres for smaller aircraft. The reactions of aircraft are dependent on their type, configuration and the speed at which they encounter turbulent zones. Refer www.bom.gov.au for more detail.

[37]    Analysis of track data for this aircraft indicated it had passed about 1.8 km abeam (north-west) the accident site at an altitude of 4,500 ft, about 1 minute prior to the accident. Therefore, aircraft-induced turbulence was considered not to be a factor in this occurrence.

[38]    RHC safety notice SN32 included: ‘what is considered significant turbulence will depend on pilot experience and comfort level’.

[39]    ATSB’s analysis of the available data indicated a relatively small reduction in estimated airspeed during the final stages of the flight. However, it was not possible to establish if this was an intentional action on the part of the pilot in response to encountering unexpected turbulence, a normal variation in airspeed during normal flight or an issue/malfunction affecting the helicopter and the airspeed it could maintain.

[40]    Maintenance records indicated the pilot last operated a Christen Eagle II in September 2021 and may have operated a T6 Harvard (fixed wing aircraft) for a total of about 7 hours in the previous 12 months. It could not be determined the extent to which the pilot was the pilot in command during these flights.

[41]    ATSB investigation AO-2012-021 identified that a door opening in-flight will not adversely affect control of the helicopter.

[42]    The POH stated that each R22 door weighs 5.2 lb (2.35 kg).

[43]    RHC safety notice SN-01 Inadvertent actuation of mixture control in flight detailed ‘cases have been reported where a pilot inadvertently pulled the mixture control instead of the carb heat or other control resulting in complete engine stoppage’.

[44]    RHC advised that, at maximum continuous power, the throttle is normally open about 75%.

[45]    All engines in R22 and R44 helicopters are derated in terms of maximum continuous power, by the pilot following the ‘Limit Manifold Pressure Chart’ in the respective POH. However, the engine is capable of providing more power if required, until the throttle is fully open. This was primarily incorporated to increase helicopter performance at higher altitudes, and to improve reliability and overhaul life. This is further detailed in the online articles Unlocking the mysteries of Robinson’s derated engines and No Ice, Thank You.

[46]    The carburettor air temperature and manifold pressures gauges required monitoring by the pilot as there were no warning lamps or horns that would alert the pilot to either being in the range indicative of icing.

[47]    In December 2014, RHC published service letter SL-66 Full Throttle Caution Light Kit, which offered an optional field installation kit for a full throttle caution light that illuminates when the engine is approaching full throttle. This would alert the pilot that lowering the collective may be required to avoid low rotor RPM. VH-RAS did not have this kit installed.

[48]    The R22 vertical speed indicator has a maximum indication of 2,000 ft/min.

[49]    Coning of main rotor blades: the upwards movement of the main rotor blades while they are rotating. This is usually in response to an increase in aerodynamic force as a result of a control input from the pilot. It is more pronounced at high weights and/or low main rotor speed.

[50]    R22 main rotor blade skins were changed from stainless steel to aluminium, around 2011, to reduce corrosion and disbonding and improve dent resistance. VH-RAS was fitted with aluminium blades at manufacture.

Preliminary report

Report release date: 09/12/2022

This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

The occurrence

On 1 October 2022, a Robinson Helicopter Company R22 Beta registered VH‑RAS departed Jandakot Airport, Western Australia for a private flight to an airstrip at Koorda, Western Australia. The helicopter and several aeroplanes were participating in a social flying weekend, with the pilots and their passengers following a common itinerary but operating independently.

On the morning of 2 October 2022, the aircraft departed at staggered times from Koorda, on the return flight to Jandakot (Figure 1). VH-RAS departed at about 1130 local time, with the pilot and one passenger on board. It was reported that the pilot intended to land en route at Northam Airport to refuel.

Figure 1: Flight from Jandakot to Koorda and wreckage location
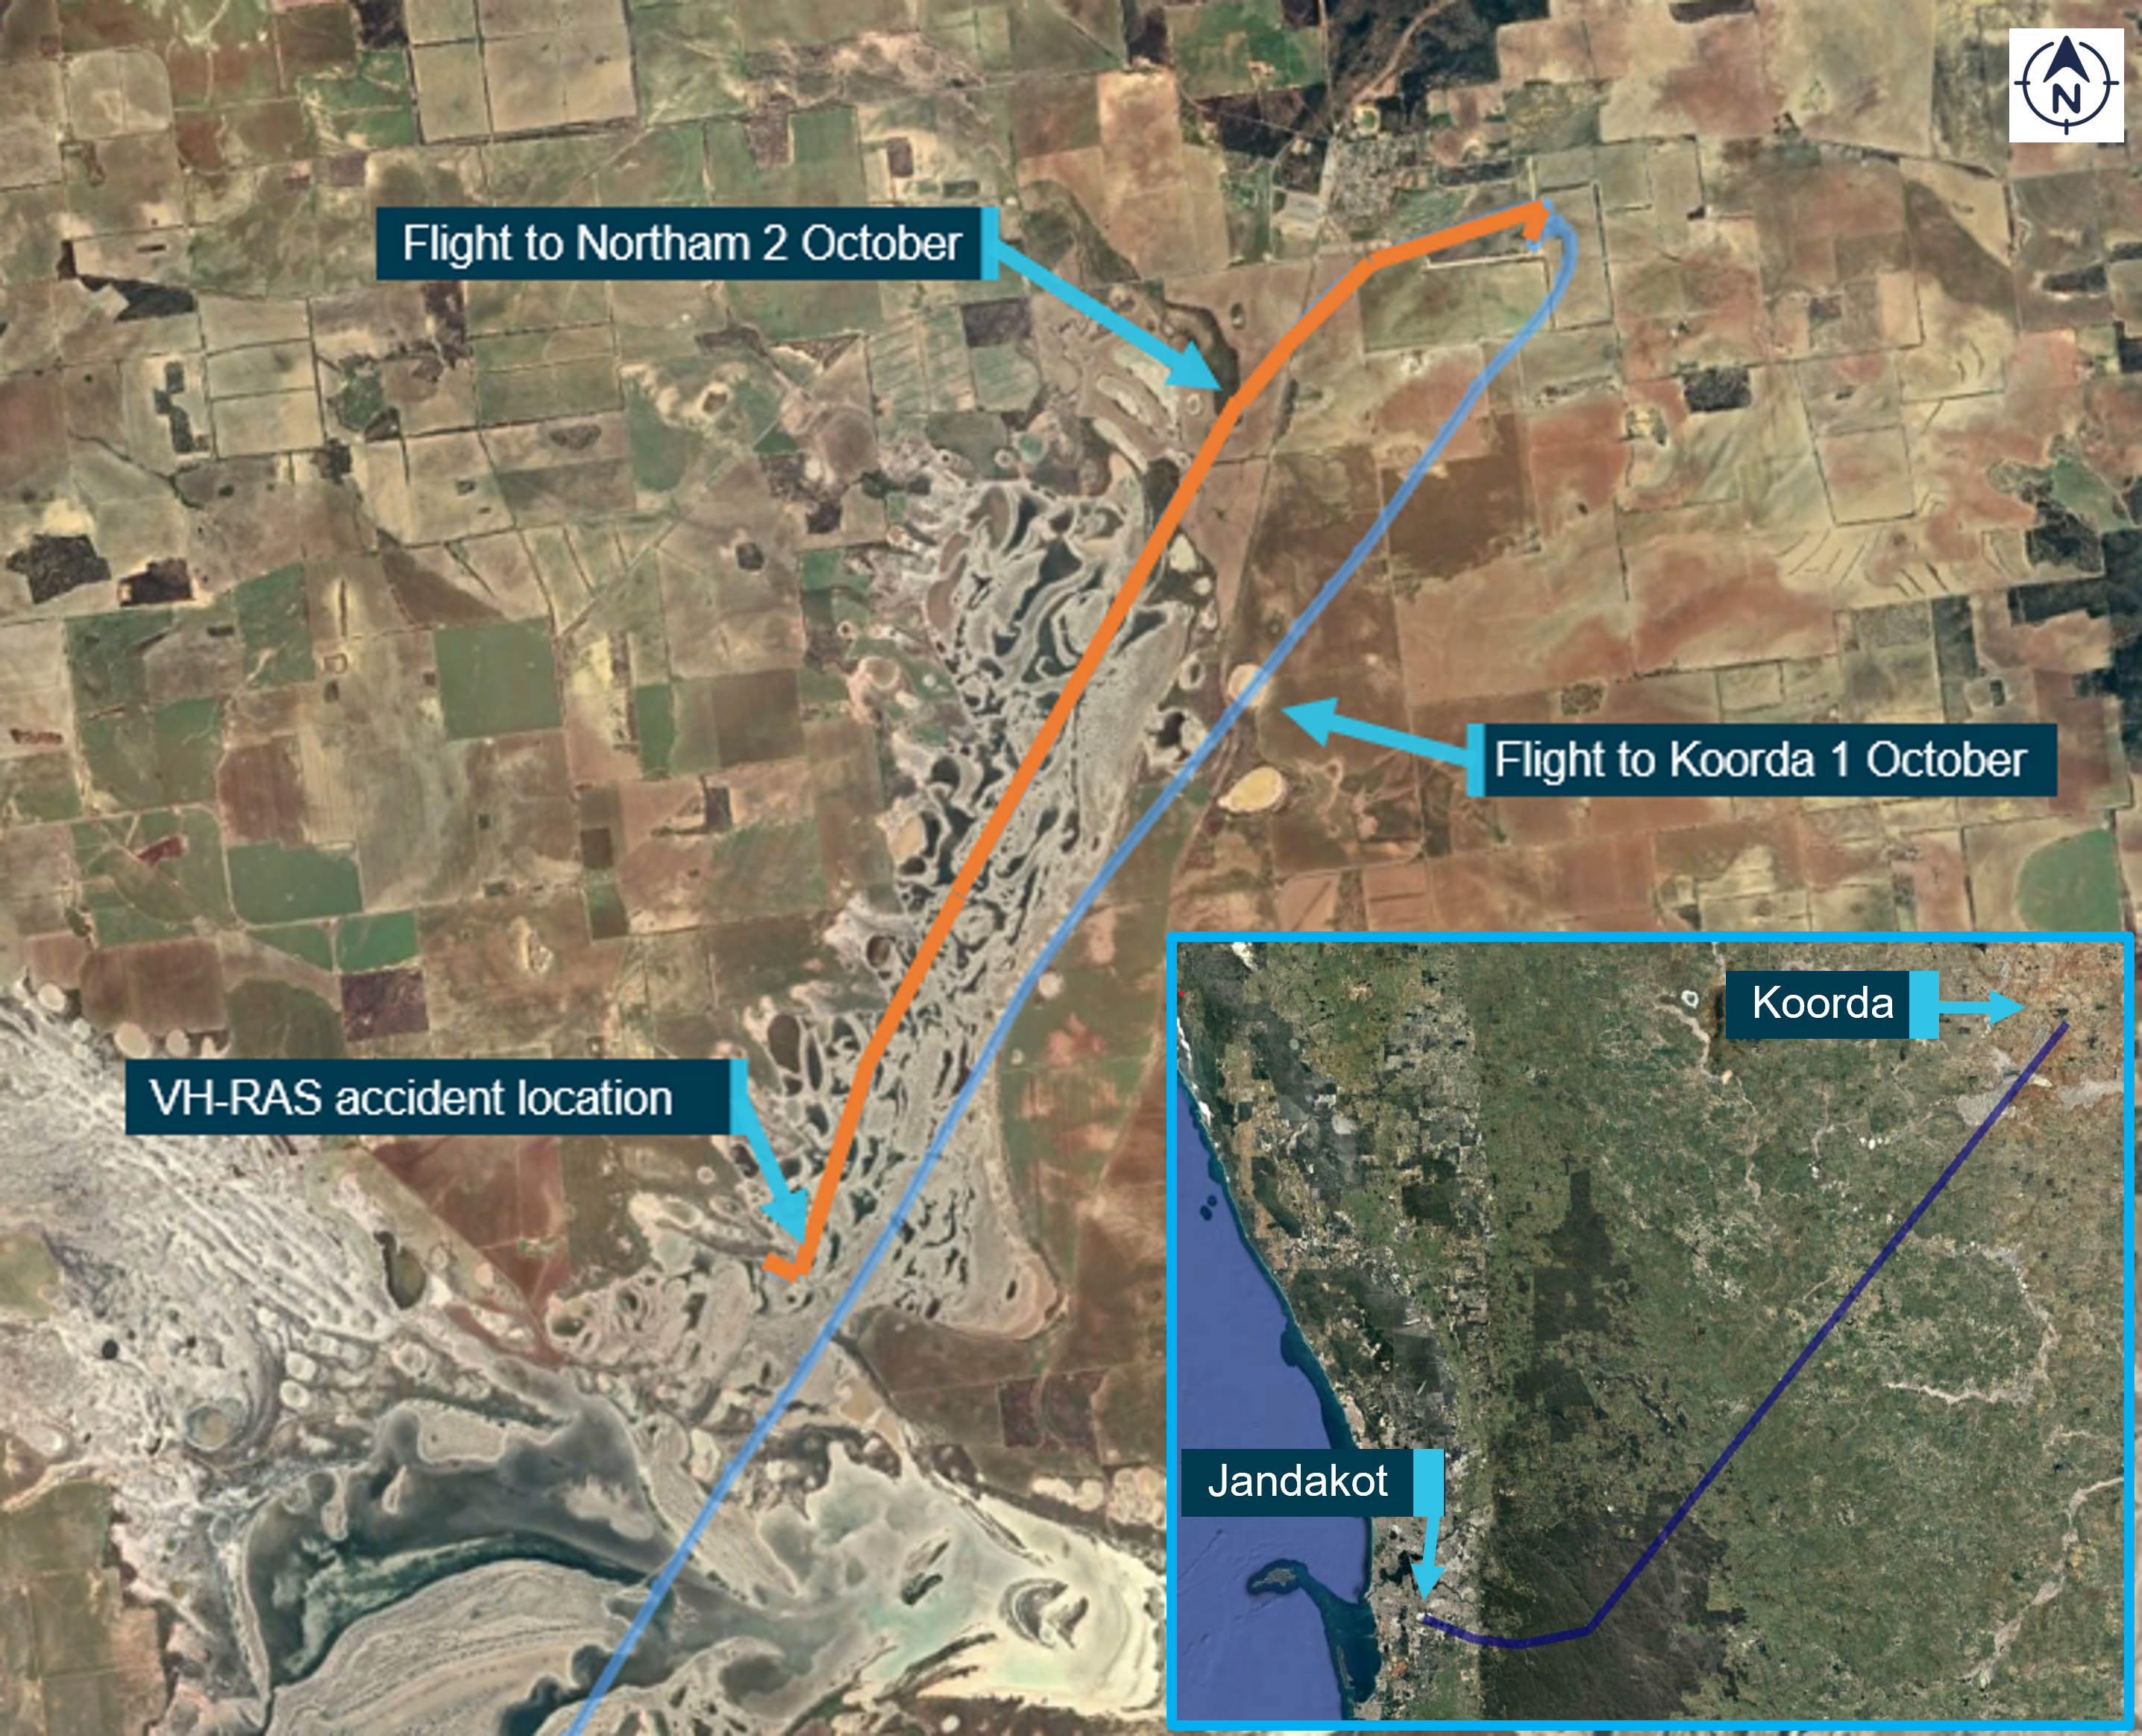
Flight from Jandakot to Koorda and wreckage location

Source: Google Earth and eTrex data, annotated by ATSB

When VH-RAS did not arrive at Jandakot as expected, a search was initiated. The wreckage was subsequently located at about 1600 that afternoon on a dry salt flat in the Cowcowing Lakes region, about 13 km south-west of Koorda. The helicopter was destroyed and both occupants were fatally injured.

Context

Pilot information

The pilot was the aircraft owner and held a valid class 2 aviation medical certificate. The pilot held private pilot licences for both aeroplanes and helicopters. At their last medical in January 2022, the pilot reported they had accrued about 3,000 hours total aviation experience (combined aeroplane and helicopter).

Passenger information

The passenger held a student pilot licence (aeroplane), with about 15 hours of dual flight experience, and a valid class 2 medical certificate.

Aircraft information

VH-RAS (Figure 2) was a 2-seat Robinson Helicopter Company R22 Beta helicopter, serial number 4617, powered by a Textron Lycoming O-360-J2A, 4-cylinder piston engine. It was manufactured in 2013 and registered in Australia the same year. It was purchased by the pilot in 2016 and had been maintained by the same maintenance organisation since that time. At the time of the occurrence, the helicopter had accrued about 2,080 hours total time in service.

Figure 2: VH-RAS

Figure 2 VH-RAS

Source: Dallas Presser

Meteorological information

The graphical area forecast prepared by the Bureau of Meteorology (BoM) indicated visual meteorological conditions were expected during the flight to Jandakot. Winds were forecast to be generally east-south-easterly below 5,000 ft, between 15–20 kt. There were no SIGMET[1] or AIRMET[2] warnings applicable to the flight.

An analysis prepared by the BoM indicated a high-pressure system was situated to the south‑west of Western Australia, producing moderate east to south-easterly winds in the vicinity of the accident site. Satellite imagery and measurements from the Bureau’s weather station at Cunderdin (about 80 km south of the accident site) indicated scattered cloud[3] could be expected at the accident site, with bases approximately 4,500–5,000 ft. There was the possibility of some thermal turbulence as the surface temperature and cloud base increased during the day, with a well-mixed air layer below the cloud. The air temperature at 2,500–3,000 ft was estimated to be about 10–12 °C, with a dewpoint of about 6–8 °C. The meteorological analysis did not identify the existence of any hazardous weather phenomena in the vicinity of the accident site.

Pilots of the other aircraft in the group reported good conditions existed for the flight back to Jandakot. Those reports were generally consistent with the BoM’s analysis. There was slight variation in the pilots’ estimates of the cloud bases during their flights, those estimates ranging between 3,000–4,500 ft. The pilots also reported encountering some light turbulence during the first part of the flight, including near Cowcowing Lakes.

Site and wreckage information

The aircraft collided with terrain inverted, on a dry salt flat, on an easterly heading. The main rotor head, with blades attached, and the top portion of the mast, were located alongside the fuselage. One main rotor blade had fractured, with the outboard section located about 3 m from the main rotor assembly. The tail cone and tail rotor assembly were attached to the fuselage. The stabiliser assembly had separated and was located about 6 m from the tail cone. The auxiliary fuel bladder was intact however, the main bladder had ruptured due impact forces. There was no fire.

In early November 2022, the engine was disassembled and examined at a CASA-approved engine overhaul facility under the supervision of the ATSB. The engine condition was consistent with the engine’s recorded time in service since overhaul. No internal or external damage was identified that may have prevented the engine from operating normally prior to the accident. No defects were identified in the induction system components, core engine, or cylinder assemblies that may have affected its pre-accident operation. One magneto was operationally tested with positive results, the other could not be tested due impact damage. Both magnetos were also internally examined and tested with nil defects identified. Further, the carburettor was internally examined, and bench tested satisfactory.

Recorded data

Flight tracking data, recorded at 5‑second intervals, showed the helicopter initially tracking in a stable south-westerly direction at about 1,700 ft above ground level (Figure 3). About 5 minutes into the flight the altitude increased by about 100 ft, followed almost immediately by a rapid descent. The data stopped in the vicinity of the accident location, about 10‑15 seconds after the commencement of the descent.

Figure 3: Last one minute of recorded flight data
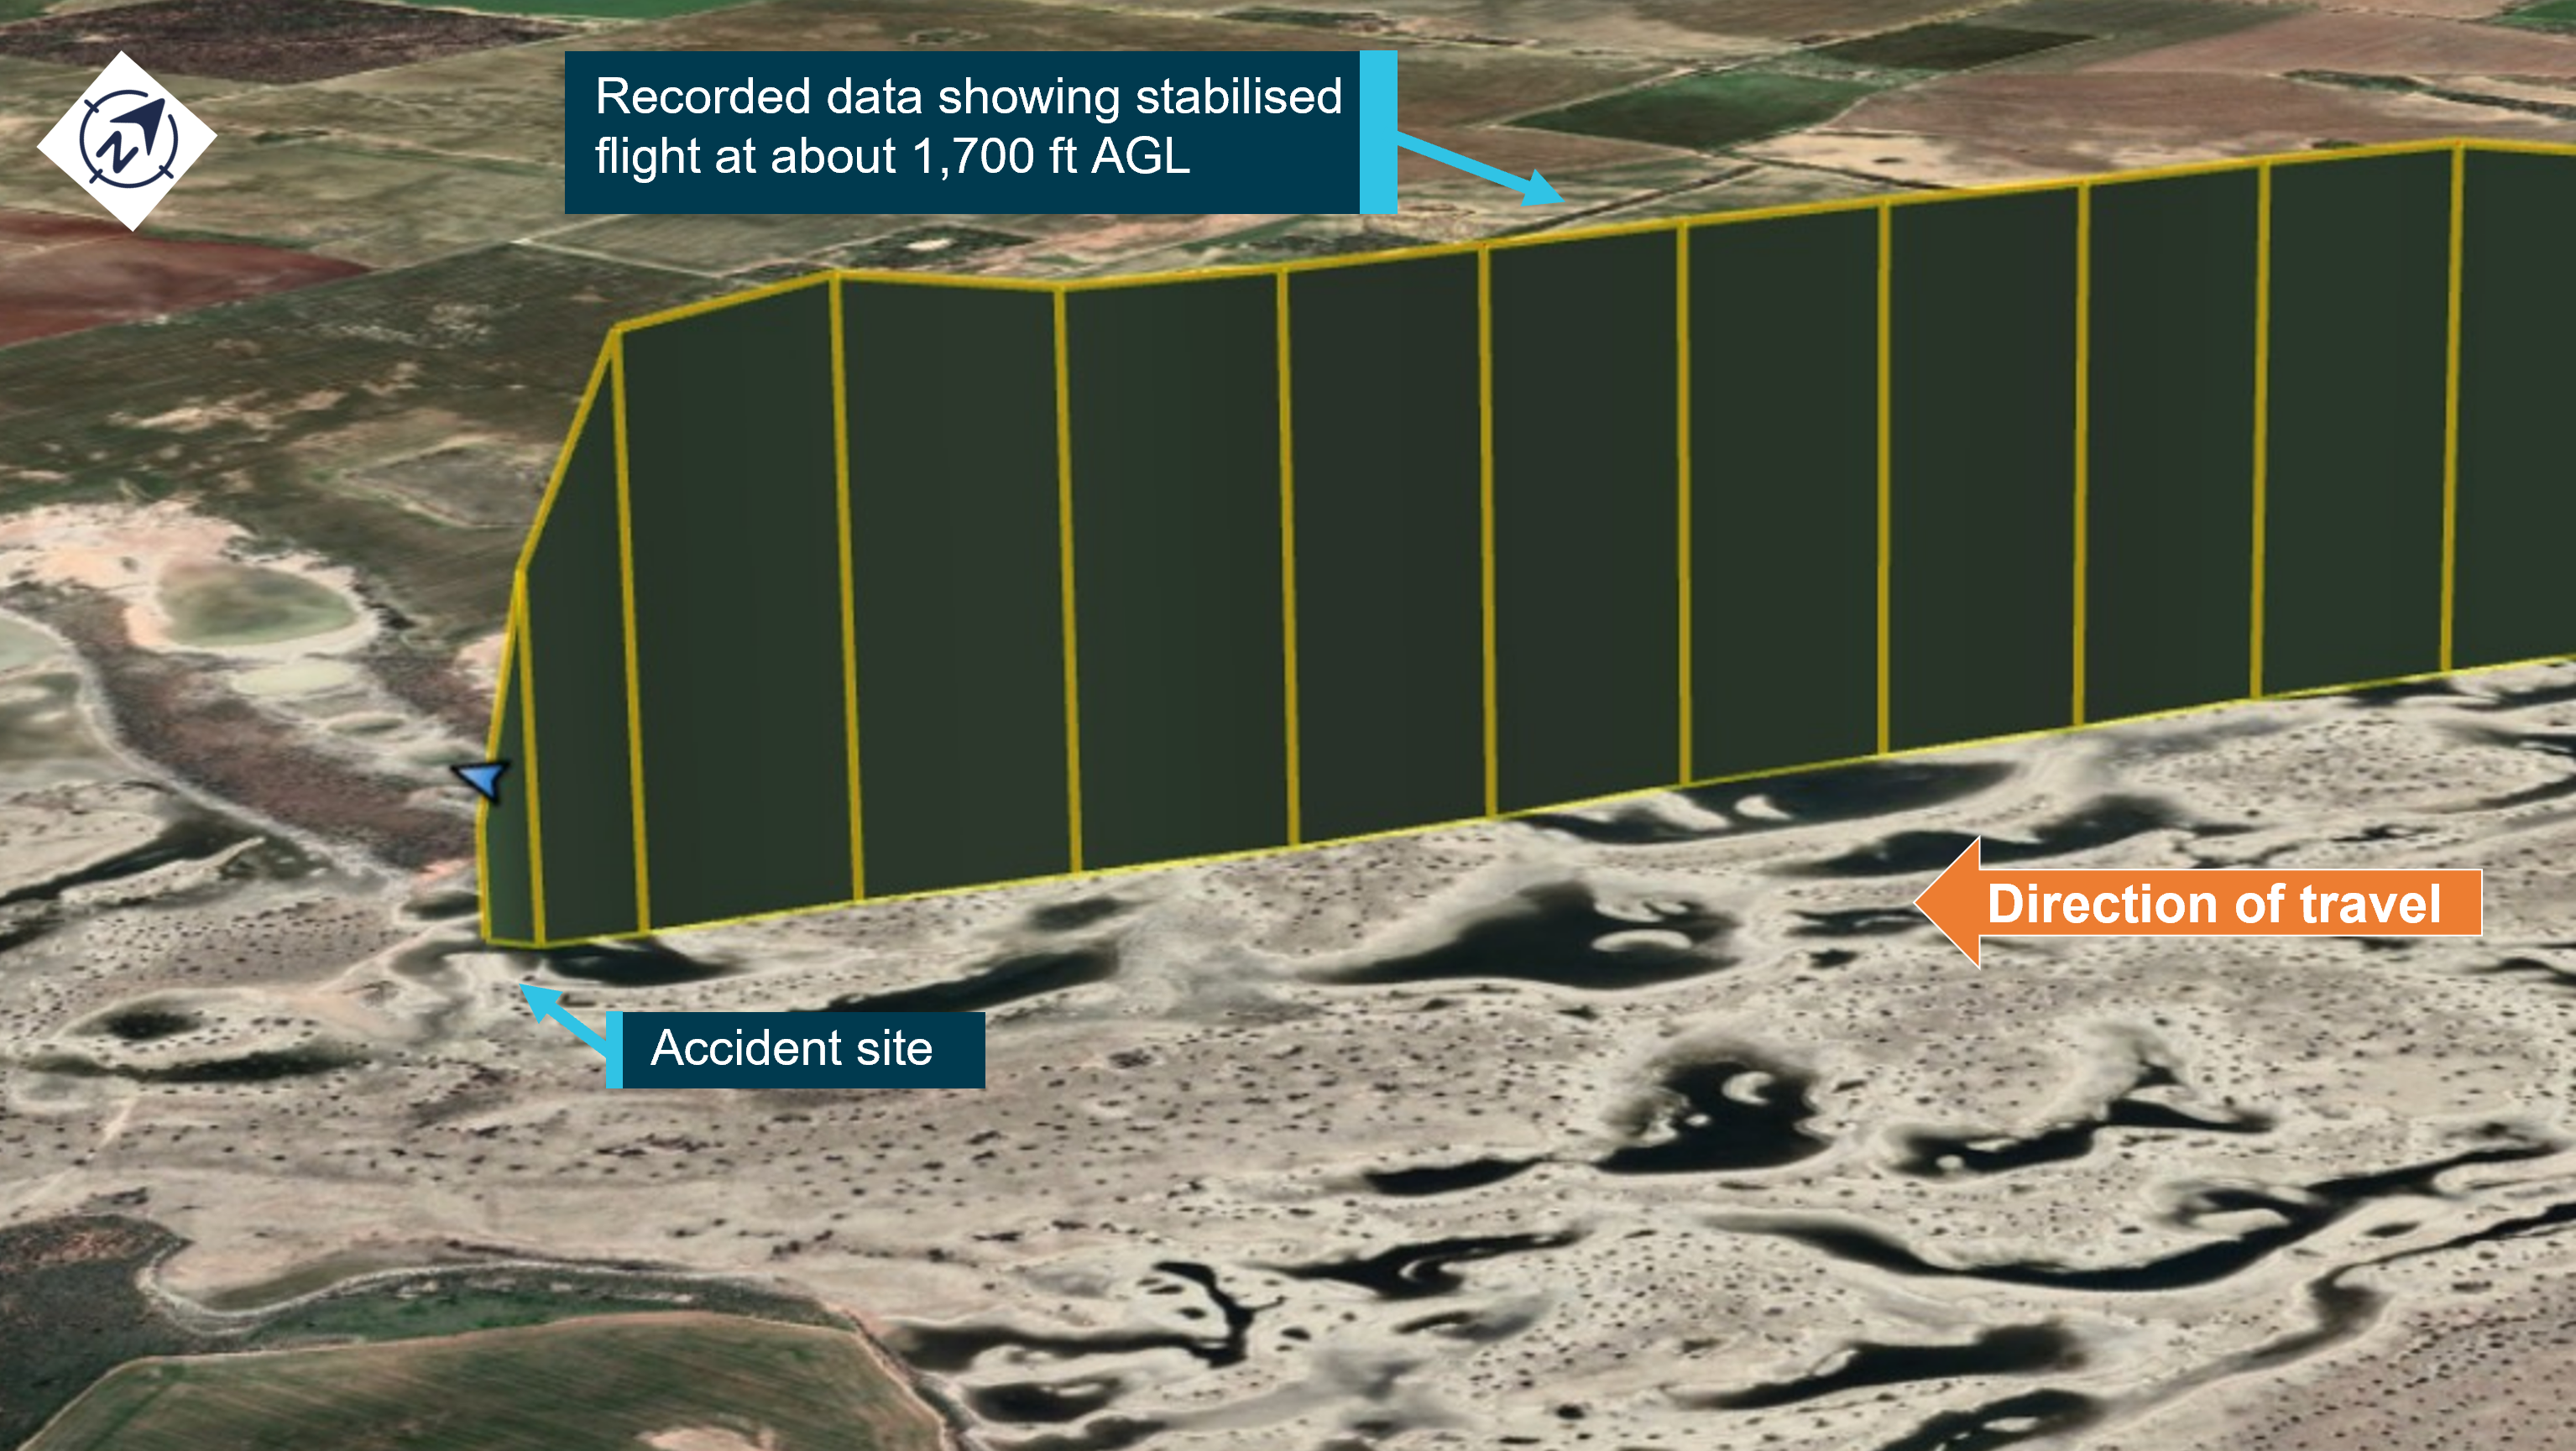
Last one minute of recorded flight data

Source: Google Earth and OzRunways data, annotated by ATSB

Further investigation

To date, the ATSB has examined the accident site and wreckage, interviewed witnesses, collected meteorological data, aircraft maintenance and pilot records, and obtained flight tracking data.

The investigation is continuing and will include further review of:

  • pilot records and medical information
  • aircraft maintenance and flight records
  • aircraft wreckage and recovered components
  • witness information
  • meteorological data
  • recorded aircraft tracking data.

Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

A final report will be released at the conclusion of the investigation.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by:           Australian Transport Safety Bureau

© Commonwealth of Australia 2022

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     SIGMET provides information on the occurrence or expected occurrence of enroute weather phenomena that are potentially hazardous to aircraft.

[2]     AIRMET provides information on deteriorating conditions, not already included on the GAF.

[3]     Scattered cloud is used to describe cloud coverage between about 3/8 and half of the sky.

Occurrence summary

Investigation number AO-2022-045
Occurrence date 02/10/2022
Location 13 km south-west of Koorda
State Western Australia
Report release date 21/05/2024
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22 Beta II
Registration VH-RAS
Serial number 4617
Sector Helicopter
Operation type General Aviation
Departure point Koorda, Western Australia
Destination Northam, Western Australia
Damage Destroyed

Collision with terrain involving Bell Helicopter 206B, VH-PHP, 6.5 km east-north-east of Maitland Airport, New South Wales, on 6 October 2022

Final report

Report release date: 25/06/2024

Executive summary

What happened

On 6 October 2022, the pilot of a Bell 206B JetRanger helicopter, registered VH-PHP, departed Casino Airport, New South Wales for a solo ferry flight to Warnervale. The helicopter flew about 30–‍60 km inland of the coast before entering the inland visual flight rules route through the Williamtown military restricted area. Before exiting the restricted area, recorded flight data showed that the helicopter deviated from the pilot’s intended track. The helicopter turned around, deviated outside the lane, and the pilot did not respond to radio calls from Brisbane air traffic control.

The pilot then flew south and exited the restricted area below 500 ft above ground level. The helicopter was then observed by multiple witnesses to be heading towards the Hunter River, descending slightly, and was possibly initiating a turn when the helicopter rolled markedly and descended rapidly, colliding with the riverbank. The helicopter was destroyed, and the pilot was fatally injured. 

What the ATSB found

Having discounted a number of other scenarios to explain the accident, the ATSB found that it was likely the pilot experienced an incapacitating event. 

Less than 12 months prior, the pilot had undergone a review by a cardiologist that determined the pilot had minor coronary artery disease and was at a low to intermediate risk of a cardiac event. However, the pilot’s post-mortem showed they had severe coronary atherosclerosis within all 3 major coronary arteries with at least 80% blockage observed within each artery. While it was not possible to forensically determine if the pilot experienced a heart attack prior to the accident, it remained a significant risk factor for the pilot.

It was also established that the pilot did not declare a significant surgery and was taking numerous prescribed, non-prescribed, and recreational drugs, which had the potential to adversely affect their performance. Further, these were not declared to the Civil Aviation Safety Authority during their aviation medical examination, which prevented a specialist assessment of the aeromedical significance of the surgical outcome, nor the medication’s use and the underlying conditions for which they were prescribed.

Safety message

It is a pilot’s responsibility to declare a full medical history and medication use at the time of an aviation medical examination so that the Civil Aviation Safety Authority and the designated aviation medical examiner can assess a pilot and their medications’ suitability for flying. Alternate medication may be available if current medications for existing conditions are incompatible with flying, thereby permitting the pilot to manage both their own personal risks as well as those to aviation safety.

Pilots should also remain cognisant of health and lifestyle changes and how this may affect their fitness to fly. Do not fly if feeling unwell or until fully recovered from temporary medical conditions and manage chronic conditions in association with your designated aviation medical examiner.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 6 October 2022, at about 1350 local time, the pilot of a Bell 206B JetRanger helicopter, registered VH-PHP, departed Casino Airport, New South Wales for a ferry flight to Warnervale. The helicopter was being returned to the registered operator after a long-term repair to correct hail damage and exchange life-expired parts. The pilot was the only person onboard. 

The helicopter tracked south-south-west, about 30‍–‍60 km inland of the coast (Figure 1).

Figure 1: VH-PHP flight track

Figure 1: VH-PHP flight track

Source: Google Earth and OzRunways, annotated by the ATSB

Recorded data indicated that at tracking point Wirradgurie, the pilot followed the inland visual flight rules (VFR)[1] route,[2] D589B and D589A (shaded in purple and green respectively on Figure 2), north of the Williamtown military control area (CTR) through restricted areas R583B and R578E.[3] 

At about 1547, when approaching the township of Dungog, the pilot received a telephone call[4] from a family member enquiring as to their progress. The pilot reported the helicopter was flying well, operations were normal, and they were 5 minutes from Maitland and 20 minutes from Warnervale. 

Figure 2: VH-PHP flight track (in white) through the Williamtown inland VFR route D589

Figure 2: VH-PHP flight track (in white) through the Williamtown inland VFR route D589

Source: Google Earth and OzRunways, annotated by the ATSB

At about 1556, when approaching Tocal (Figure 3), about 4 NM (7 km) from the end of the lane, the helicopter started to climb and then conducted a right 180° turn to track northbound. After about 2 minutes, the helicopter transitioned through the upper limit of the VFR lane (1,600 ft) and continued climbing to 3,100 ft. The helicopter then descended to 1,100 ft, back into D589A and continued to follow the lane northbound until Hilldale when the pilot again made a right turn. This time the pilot flew the helicopter outside the lateral bounds of the lane by conducting a gradual climbing orbit around a hill before crossing from the east to the west of the lane, reaching 2,900 ft during the transition. 

At about 1611, the helicopter then descended over the town of Vacy, flying as low as 120 ft above ground level and as slow as 22 kt ground speed before climbing and heading south. The helicopter then descended to low levels travelling parallel to, but just outside, the VFR lane western boundary until it exited the southern border of R578E at Maitland Vale.

Figure 3: VH-PHP flight track (in white) through the Williamtown VFR route D589A

Figure 3: VH-PHP flight track (in white) through the Williamtown VFR route D589A

Source: Google Earth and OzRunways, annotated by the ATSB

At about 1616, the helicopter cleared a ridge by about 200 ft and descended gradually toward the Hunter River. At the last recorded data position, the helicopter was at 300 ft and 98 kt (Figure 4).[5] 

After clearing the ridge, the helicopter was visually observed by 7 witnesses. Common features of these reports were that the helicopter headed towards the river, descended slightly, possibly initiated a turn at which point it rolled markedly, descended rapidly, and collided with the riverbank. Some of those witnesses, as well as others who only heard the helicopter and the impact, reported the helicopter sounded normal or nothing out of the ordinary, while others reported it sounded rough or the engine was ‘screaming’. 

The helicopter came to rest on a muddy river flat near the water’s edge. A first responder stated there was smoke coming from an engine fairing grille. They found a fire extinguisher in the cabin, discharged it into the grille and the smoke stopped. The helicopter was destroyed, and the pilot was fatally injured. 

Figure 4: VH-PHP final flight track

Figure 4: VH-PHP final flight track

Source: Google Earth and OzRunways, annotated by the ATSB

Context

Pilot information

The pilot held a Commercial Pilot Licence (Helicopter) and was qualified to fly by day under the visual flight rules (VFR). The pilot’s paper logbook indicated a total of 382.9 hours aeronautical experience, of which 132.5 hours were in various Bell 206 model helicopters. However, the last entry in this logbook was December 2003. No other paper or electronic logbooks could be found. The pilot indicated in their last aviation medical examination in October 2021 that they had 7,200 total flying hours and no hours recorded in the prior 12 months. Prior medical questionnaires recorded hours that appeared to be steadily increasing and rounded to the nearest 100 hours. The pilot had an OzRunways[6] account, which indicated they had accrued 27 hours since May 2017 while using their OzRunways application. The application recorded:

  • 11.6 hours over 11 flights in 2017
  • 1.0 hours over 2 flights in June 2018
  • 11.9 hours over 17 flights in 2022.

In the 90 days prior to the accident, no flights were recorded by the application. 

The pilot last conducted a single-engine helicopter flight review on 26 January 2022 that was valid until 31 January 2024. This flight was conducted in the accident helicopter. In interview, the flight instructor stated the pilot was ‘reasonably cautious, not overconfident’ and they were ‘not out of practice’. 

The pilot held a Class 1 and Class 2 Aviation Medical Certificate issued by the Civil Aviation Safety Authority (CASA). The Class 1 medical was valid until 26 October 2022 and the Class 2 valid until 26 October 2023. The pilot was required to have reading correction eyewear with them while flying.

The pilot had recently returned from an overseas holiday and had a head cold. A family member reported the pilot had 8 hours sleep the night before the flight and in the morning was in good spirits and appeared to have improved with respect to their head cold. 

Helicopter information

VH-PHP was a Bell Helicopter Company, model 206A that was manufactured in 1970 in the United States. The helicopter was first registered in Australia in May 1986. In 1988, the helicopter was rebuilt and converted to a 206B model with fitment of a Rolls Royce/Allison 250-C20 turboshaft engine and the associated uprated transmission, rotor head and other required changes. 

In 2019, the helicopter was damaged by hail and repaired over a 3-year period. During this time, other modifications were performed, including correcting issues associated with the A to B model conversion. In April 2022, as part of a maintenance test flight, the helicopter was flown from Warnervale to Casino. During the test flight, a ‘lazy’ power turbine governor was identified. Subsequently, further parts required repair or overhaul, including time-expired parts. 

A 30 minute maintenance test flight associated with the replacement of components was conducted and the helicopter was found to be in a satisfactory condition. A maintenance release was issued, and the helicopter flew the following day with the aim of returning to Warnervale (the accident flight).

Meteorological information

In the days before the accident, the east coast of Australia had been under the influence of a low‑pressure system, which had included large quantities of rain in some areas.

The Bureau of Meteorology graphical area forecast, current for the accident flight, indicated greater than 10 km visibility and broken cloud[7] with a base of 4,000 ft above mean sea level on departure from Casino. However, shortly after taking off, the pilot was to fly into an area with isolated rain, 6,000 m visibility and scattered cloud with a 2,000 ft base. Further south along the flight path taken, the weather was forecast to have visibility greater than 10 km but reduced to 5,000 m and 2,000 m in scattered rain and showers. Broken cloud was forecast throughout these varied conditions. 

At 1600, the aerodrome meteorological report (METAR)[8] for Maitland Airport (about 6 km west‑south-west from the accident site) recorded 8 kt of wind, visibility greater than 10 km, scattered cloud at 4,000 ft and 4,500 ft, and overcast cloud at 7,800 ft. The air temperature was 21 °C.

Two eyewitnesses separately reported seeing the helicopter, one as it operated down the D589A and the other when it was in the R578E restricted area. These witnesses reported the weather at the time to be a mid to high level overcast cloud with no rain. A retired airline pilot in the area of the accident site stated that the weather was suitable for VFR operations.[9] They observed a general base layer at 5,000 ft, and scattered cloud with patches to the south.

Recorded information

Position data

The helicopter had analogue instrumentation and had no fitted equipment that recorded data. The pilot was using the OzRunways application on their mobile phone. The application sent position information back to a server via a mobile data connection. Position, altitude, and ground speed was recorded for the entire accident flight at about 5 second intervals (refer to Figure 2, Figure 3 and Figure 4).

Radio communications

The Airservices Australia area frequency radio calls were reviewed. The pilot made no calls on the appropriate area frequencies for the flight, nor were they required to do so. At 1605, Brisbane Centre air traffic control made 3 calls trying to contact the pilot in response to the helicopter flying through restricted airspace R578E, with no response received. 

No distress calls were made on the area frequency around the time of the accident. 

Mobile phone

Mobile phone records showed that the pilot made and received multiple calls during the flight. Some calls were from family members checking on the pilot’s progress. At 1614, the pilot missed a call and received a missed call text. Also at 1614, the pilot received and answered a call from an unknown person for 27 seconds. The call ended about 60 seconds before the accident. Despite numerous attempts, the ATSB was unable to establish contact with this caller to seek any further information on the situation with the pilot at that time. 

Wreckage and impact information

An initial assessment of the helicopter was conducted on the riverbank, however, due to rapidly rising river levels, the wreckage was moved to higher ground and the principal components were moved to a secure location for further examination. 

The wreckage trail was about 45° to the right of the last track direction recorded by the pilot’s OzRunways application (Figure 4). Examination of the accident site showed the wreckage trail (Figure 5) had started at a tree and extended along the riverbank for a distance of 33 m on a heading of 210° (magnetic). Figure 5 also shows the location of key components including the main rotor hub and blades, right horizontal stabiliser, right cockpit door, tail rotor blades, tail gearbox, left skid, and the fuselage.

Some lower branches of the tree (Figure 6) were cut at 75° from the horizontal and the multiple cuts were at about 75° to each other suggesting they were cut by the main rotor system. Other branches higher up on the other side of the tree were snapped off in the general direction of the wreckage. 

Figure 5: Wreckage trail

Figure 5: Wreckage trail

 Source: NSW Police annotated by ATSB

Figure 6: Initial impact tree

Figure 6: Initial impact tree

Source: ATSB

All major aircraft components were accounted for at the accident site except for 2 parts of a main rotor blade. There was no evidence of a birdstrike identified in the wreckage. 

The turbine and combustion sections of the engine had partially separated from the gearbox section. The left compressor discharge tube had separated from the compressor section at the compressor output flange. The right compressor tube was partially crushed between the combustion section and compressor section, consistent with the right side of the fuselage impact with terrain. The exhaust pipes were removed and a visual inspection of the output face of the power turbine was carried out with no defects evident. Due to the level of disruption to the engine and compressor casings, rotation of the power turbine and compressor was not possible. 

The engine fuel and oil filters were removed and inspected with no unusual contamination found. The engine oil tank was punctured at the bottom of the tank by the tail rotor driveshaft. The puncture exhibited signs of rotation of the driveshaft and remnants of engine oil were found in the tank.

Fuel was found spilled at the accident site and fuel in the fuel filter bowl showed no evidence of contamination with water.

The main rotor hub was intact and attached to the mast section. The mast nut was installed and locked, and there were minimal signs of mast bumping.[10] Both main rotor blades were still attached to the rotor head.

The 2 parts unaccounted for were a 2 ft long outboard section of the main rotor blade leading edge and the associated blade tip weight. It was assessed that the leading edge and tip weight were likely projected into the swollen river during the impact sequence due to the helicopter heading, the pattern of damage, and fracture surfaces of the recovered adjacent leading edge, trailing edge and tip sections.

The main rotor mast was fractured near the main rotor head. The fracture surface was indicative of an overload failure. The main transmission was free and smooth in rotation. No oil was present due to the fracture of the oil filter mount, however, there was residual oil evident in the gearbox and the oil chip detector was removed and inspected with no signs of internal failure evident. The oil filter was opened and inspected with no signs of unusual contamination present.

The upper surface of the main rotor gearbox isolation mount had heavy scoring, caused by the rotating engine driveshaft during the impact sequence and the main gearbox input flange was radially scored through about 225° in a periodic saw-tooth pattern. This indicated that the engine was driving the driveshaft, and the main gearbox input flange were rotating at the time of separation.

In summary, examination of the helicopter’s flight controls, engine and structure did not identify any pre-existing defects that would have affected normal operation. 

Survival aspects

The helicopter cabin underwent severe disruption upon impact with terrain. The front row seats were fitted with a 4-point harness. Evidence showed the pilot was wearing the safety harness correctly but due to the severity of the impact with the ground, the restraint system failed. The pilot was not wearing a helmet.

The accident was not considered survivable, and the pilot received non-survivable injuries.

Operational information

The pilot did not submit a flight plan, nor were they required to do so. The track taken was 30 to 60 km inland from the New South Wales coast, which allowed the pilot to fly under Class E and Coffs Harbour Class C controlled airspace.

At tracking point Wirradgurie, the pilot followed the inland VFR route west of Williamtown (Newcastle) Airport. The VFR route, designated in 2 segments as D589B and D589A, is a 2‍–‍3 NM (4‍–‍6 km) wide lane under restricted airspace from ground level to 2,500 ft above mean sea level and ground level to 1,600 ft respectively. The VFR lane enables pilots to visually fly under restricted areas R583B and R578E (military flying area) without requiring permission or monitoring by Williamtown airspace controllers.

The 2 eyewitnesses who observed the helicopter in D589A and R578E both reported that it appeared to be operating normally. There were other aircraft in the vicinity operating at higher altitudes both in R578E and in the Class G airspace just to the south of the restricted area. However, VH-PHP was the only aircraft broadcasting a transponder signal in the D589 inland VFR route at the time.

A family member who spoke with the pilot during the flight stated they were not aware of any reason why the pilot would have diverted from the intended track. Based on the assumed flight path and prior cruising ground speed, the estimated times given by the pilot of 5 minutes to Maitland and 20 minutes to Warnervale were broadly correct. However, when the subsequent deviation was included, the ATSB estimated the times to Maitland and Warnervale would have been closer to 29 minutes and 44 minutes respectively.

Medical and pathological information

Post-mortem examination

The forensic pathologist who conducted the post-mortem examination concluded that the pilot received fatal injuries sustained during the accident. However, they also noted severe triple vessel coronary artery disease with at least 80% lumen[11] stenosis[12] observed within each artery. The post-mortem report stated that:

Severe coronary artery disease is a risk factor for sudden death due to myocardial ischaemia[13] and subsequent fatal arrhythmia.[14]

However, the report also stated there were:

No features of acute myocardial infarction.[15]

Toxicological results from a post-mortem subclavian blood sample revealed the following medications, which were considered ‘non-fatal’ levels: alprazolam (<0.005 mg/L), diazepam (0.13mg/L), and metabolites nordiazepam, temazepam and oxazepam. Citing Baselt (2020), the forensic pathologist noted that: 

Although alprazolam and diazepam were detected at non-lethal levels, they are both central nervous system (CNS) depressant medications which may act synergistically to cause sedation, confusion and incoordination.

Methylecgonine (0.13mg/L) a cocaine metabolite, Levamisole (a common cutting agent of cocaine) and cannabinoids (delta-9-tetrahydrocannabinol (THC) 0.006 mg/L and THC acid 0.004 mg/L) were also detected. Carbon monoxide saturation was less than 1% and no alcohol was detected.

Coronary artery disease 

During the post-mortem examination, the pilot’s heart was found to have severe coronary atherosclerosis[16] within all 3 major coronary arteries (the left anterior descending coronary artery, circumflex artery and the right coronary artery) with at least 80% lumen stenosis observed within each artery. Histological examination confirmed the severe atherosclerosis within all 3 main coronary arteries, with 75-90% arterial lumen stenosis observed. Focal perivascular fibrosis[17] and occasional enlarged myocytes[18] were seen, which are both associated with the development of cardiac dysfunction.

In coronary artery disease, one or more of the coronary arteries are partially blocked by plaques. If a plaque breaks open, it can cause a blood clot in the heart, which can lead to a heart attack (also known as a myocardial infarction). They occur when the heart has either a sudden interruption of blood supply, or a longer term reduced blood supply, both of which cause damage to the heart muscle. 

Signatures of a heart attack in survivors, such as heart inflammation and fibrosis (scarring) take time to develop and are not normally present in people who immediately succumb to the heart attack or an associated fatal event. Therefore, it may be challenging to identify a heart attack as the reason for an accident when sudden death occurs. 

There are 3 types of heart attack. The most severe form is ST segment elevation myocardial infarction. It has the classic symptom of pain in the centre of the chest and may range from discomfort to debilitating. Other symptoms may include shortness of breath or trouble breathing, nausea, heart palpitations, anxiety, sweating, and feeling dizzy, lightheaded, or fainting. 

The CASA fact sheet on coronary artery disease, noted that the disease is associated with distracting pain, acute shortness of breath, arrhythmia and sudden death. When considering the effect on flying, CASA indicated that ‘Stressful phases of flight can force the cardiac system to work harder. The sedentary nature of aviation can also be detrimental to this condition.’

The ATSB’s aviation medical specialist’s opinion was the pilot was at risk of a sudden incapacitating cardiac event. They had advanced triple-vessel coronary artery disease, capable of inducing incapacitating and distracting chest pain with or without an arrhythmia, such as ventricular tachycardia[19] or ventricular fibrillation.[20] This can induce severe and incapacitating chest pain leading to distraction and declining consciousness. 

Medical history

The pilot had ongoing treatment for chronic insomnia with various medications being prescribed. They underwent a sleep study in 2016 and was found not to suffer from sleep apnoea. At the time of the accident, the pilot was prescribed 2 alternating medications for the insomnia: Alprazolam 2 mg and Amitriptyline hydrochloride 25 mg. Only Alprazolam was found in the pilot’s toxicology. The pilot had also previously been prescribed Stilnox for their insomnia. 

The pilot also had a history of elevated blood pressure. Treatment had included medication although this stopped during a period of weight loss. The pilot had since regained weight but had not resumed treatment for high blood pressure.

In 2015, the pilot underwent spinal fusion surgery to correct pain associated with osteoarthritic degeneration of the lumbar spine. In 2020, the pilot underwent re-exploration surgery with the removal of existing intervertebral fusion cages and replacement with new ones. The family advised that this surgery was successful and greatly improved the pilot’s life.

Aviation medical examinations

The pilot had seen the same designated aviation medical examiner (DAME) for many years and medical examinations. In August 2018, the pilot failed a medical examination due to their diastolic blood pressure level.[21] The pilot reapplied for an aviation medical in May 2019 and passed the examination.

In October 2021, their Class 2 aviation medical certificate was due to expire and they attended a consultation with their DAME for a Class 1 and Class 2 medical examination. The pilot passed their examination based on the responses to the pre-medical questionnaire and the testing prescribed by CASA. These tests included an audiogram, a resting electrocardiogram, and a glucose and lipids blood test.

During a Class 1 medical examination, a DAME will enter updated information into the CASA medical record system, which calculates the risk score of an applicant using the CASA coronary heart disease risk factor prediction chart. The chart and an associated formula provide a cardiac risk index. Risk factors include age, high-density lipoprotein and total cholesterol levels, systolic blood pressure, and whether the person is a smoker, has diabetes or left ventricular hypertrophy.[22] A score above 14 triggers the requirement for further investigation starting with a stress electrocardiogram. During their most recent medical examination, the pilot did not score above 14.

The pilot declared in their questionnaire a lower back operation in 2015 and magnetic resonance imaging associated with that operation in 2016. The DAME assessed the pilot’s remaining range of motion to be adequate. In addition, they declared the sleep study undertaken in 2016. The pilot did not declare any ongoing medical issues, recent surgeries, nor that they had taken any prescribed medications in the last 4 years. The DAME had no other resources available to validate the pilot’s response that they were not taking prescription medications.

While the pilot passed their aviation medical exam, in discussions with the DAME, they decided the pilot should be referred for another sleep study and a cardiologist review. This was based on their current job stressors, history of weight fluctuations, history of high blood pressure, high cholesterol, and poor lipid control, and having been 5 years since their previous testing. 

The pilot attended an appointment with a cardiologist in November 2021. The cardiologist reported that there was no evidence for significant heart disease and the pilot was at low risk of a significant cardiac event. As the pilot was unable to complete the stress electrocardiogram due to back pain, they were referred for a computed tomography (CT) coronary angiogram. The angiogram report stated a moderate burden of coronary artery calcification with plaques in all areas. In addition, it was reported that the pilot had only minor coronary artery disease (less than 25% narrowing), however, mixed plaque in the proximal third of the left anterior descending artery caused up to 25‍–‍49% narrowing. The report also stated the pilot had a poor calcium score of 340, which was in the ninetieth percentile for the pilot’s age and gender.

Civil Aviation Safety Authority requirements  

A pilot is required to declare to CASA when they have a medically significant condition that affects them for a period of time and to stop acting as authorised by their licence while that condition continues. If the condition becomes chronic, the DAME, in consultation with CASA, may be able to treat the condition such that the pilot again meets the medical standard. CASA provides guidance for pilots on their website on the process and obligations.

CASA lists the classes of medications that can have side effects, which may impair flying performance and groups them into 4 levels, categories A through D (Table 1).

Table 1: CASA medication categories 

Table 1: CASA medication categories

Category D broadly includes some conditions or classes of medications that can treat conditions such as, but not limited to, angina, cancer, Parkinson’s disease, hypertension, malaria, psychiatric conditions, seizures, smoking cessation aids, steroids and weight loss medications. It also includes Therapeutic Goods Administration Schedule 8 controlled substances.[23]

CASA advised the ATSB that alprazolam, amitriptyline hydrochloride and diazepam are classed as category D. They stated this was due to the side effects of the medications themselves or for the conditions in which they were treating. Alprazolam is a Schedule 8 controlled substance, while diazepam is a Schedule 4D restricted substance.[24] Stilnox is a category B medication, which was approved for use with the restriction of a short no fly period after ingestion.

CASA advised they can access the Medicare Benefits Schedule and Pharmaceutical Benefits Scheme to check an applicant’s history when it has reason to, such as when incomplete medical information is supplied by the applicant, for complex medical certifications, or for monitoring compliance with certain medications. 

For the awareness of pilots, CASA publicises a limited list of approved medications, along with a list of medications that are considered hazardous or prohibited in aviation.[25] Medications that are considered as hazardous can only be used with the express clearance of CASA or a DAME. 

Pharmacological influence

The post-mortem report was examined by a consultant forensic pharmacologist at the request of the ATSB. The review noted that the detection of THC and THC acid could have only occurred as a result of the use of cannabis. Specifically, the consultant concluded that, with the blood concentration[26] of diazepam and THC detected, some impairment of the high-level psychomotor skills required for flying would be expected and could not be excluded as being factors in the accident. 

In 2012, the National Safety Council Committee on Alcohol and Other Drugs stated that it was unsafe to operate a vehicle or other complex equipment while under the influence of cannabis, its primary psychoactive component THC or synthetic cannabinoids with comparable cognitive and psychomotor effects. They reported that studies have demonstrated that cannabis intoxication produces dose-related impairment of cognitive and psychomotor functioning and risk-taking behaviour. They also reported the growing epidemiological evidence that detectable THC concentration in blood is associated with increased motor vehicle crash risk, particularly above THC concentrations of 0.002 mg/L.

The opinion of the forensic pharmacologist was the relative concentration of diazepam to the nordiazepam, oxazepam and temazepam concentrations in the pilot indicated they most likely used diazepam within 12 hours to 24 hours of the accident. The therapeutic range for diazepam is 0.1 to 2.0 mg/L.

Epidemiological and experimental studies have demonstrated benzodiazepines (a class of drug that includes diazepam) impair psychomotor skills performance. There is an epidemiological association between benzodiazepine use, increased motor traffic-accident risk and responsibility of the drivers for the crash (Longo et al., 2001; Bramness et al., 2003; Smink et al., 2008).

The pharmacologist also noted that there was no cocaine or benzoylecgonine (a major metabolite) reported to be present in the pilot’s blood but the cocaine metabolite methylecgonine was detected. They further stated that, while this confirmed the pilot had used cocaine within the previous few days, methylecgonine does not produce impairment although the possibility of impairment due to the ‘crash phase’ or withdrawal phase could not be excluded as being a possible factor in the accident. Cocaine effects on skills performance include risk-taking, inattentiveness and poor impulse control. In the withdrawal phase, the user can experience fatigue, sleepiness and inattention (Couper & Logan, 2014 Revision).

Alprazolam can also impair psychomotor skills (Baselt, 2001) and even at therapeutic blood concentrations, it can cause profound impairment of psychomotor skills required for complex tasks such as driving (Verster et al., 2002; Bramness et al., 2003; Leufkens et al., 2007). However, the pharmacologist indicated that, at the level detected, it was unlikely there would have been impairment of the pilot’s psychomotor functions and it unlikely contributed to the accident.

The ATSB’s aviation medical specialist indicated that the presence and levels of these psychoactive drugs and prescription medications would not have increased the risk of heart attack.

Medical-related accident research 

ATSB research report B2006/0170

The ATSB’s research report (B2006/0170) on Pilot Incapacitation: Analysis of Medical Conditions Affecting Pilots Involved in Accidents and Incidents 1 January 1975 to 31 March 2006 (Newman, 2007) found pilot incapacitation due to the effects of a medical condition or a physiological impairment represents a serious potential threat to flight safety. A search of the ATSB’s accident and incident database was conducted for medical conditions and incapacitation events between 1 January 1975 and 31 March 2006. Heart attack was the fourth highest form of pilot incapacitation behind gastrointestinal illness, smoke and fumes, and loss of consciousness.

There were 98 occurrences in which the pilot of the aircraft was incapacitated for medical or physiological reasons and in 10 occurrences (10.2%), the outcome of the event was a fatal accident. All the fatal accidents involved single-pilot operations, and in the majority of cases, heart attack was the cause. The second highest cause was loss of consciousness.

The results of this study demonstrated that the risk of a pilot experiencing an in-flight medical condition or incapacitation event was low. However, if the pilot experienced a heart attack the risk of a fatal accident occurring increased. The report also suggested that the aeromedical certification process must keep pace with the evolving nature of modern medical science to ensure that the risk of in-flight incapacitation remained low.

United States Federal Aviation Administration Office of Aerospace Medicine (DOT/FAA/AM‑18/8)

This study, DOT/FAA/AM-18/8 of Incidental Medical Findings in Autopsied U.S. Civil Aviation Pilots Involved in Fatal Accidents (Ricaurte, 2018) examined incidental medical findings (IMFs) reported in the autopsies of pilots who died in United States aircraft accidents from April 2013 through March 2016. Incidental medical findings are previously undiagnosed medical conditions that were incidentally discovered during the autopsy, which may or may not have been related to the cause of death or of the accident. 

Out of the selected pilots, 42% were found with IMFs reported in the autopsy. Cardiovascular abnormalities were the most common IMF (85%). The National Transportation Safety Board determined a medical issue was either the probable cause or a contributory factor in 12.2% of accidents with IMFs. The report noted that, while in commercial operations with 2 pilots, the other pilot carries out the flying duties, in single pilot operations, the outcome of the event is usually catastrophic. Epidemiological studies showed that in 15% of patients with coronary heart disease, sudden cardiac death is the initial coronary event.

Similar occurrences

ATSB investigation AO-2008-021

On 18 March 2008, a Pitts S-2A aircraft impacted the ground 7 km north-east of Camden, New South Wales, fatally injuring the occupant of the rear cockpit. The occupant of the rear cockpit, an experienced aerobatic pilot, was undergoing a routine flight review with an instructor. During a practice forced landing, the pilot stopped responding to instructions and commands, so the instructor took control of the aircraft. A powerful nose-up force began acting on the control column and the aircraft entered an incipient aerodynamic stall.[27] The instructor recovered the aircraft from the stall but, this came too late to prevent a collision with trees. Post-mortem examination of the pilot found they had severe heart disease. Expert medical opinion considered it likely that the pilot experienced an incapacitating event as a result of their heart disease.

ATSB investigation AO-2010-004

On 22 January 2010, a Victa Airtourer 115/A1 was landed safely on Miles Beach, Bruny Island, Tasmania. The pilot, being the sole occupant, shut down, exited and secured the aircraft before leaving it on the beach and walking away. The pilot was found deceased about 300 m from the aircraft. A post-mortem revealed the pilot had died as the result of a heart attack.

ATSB investigation AO-2018-057

On the afternoon of 17 August 2018, the pilot of a Kawasaki Heavy Industries BK117 helicopter was conducting fire-bombing operations approximately 9 km west of Ulladulla, New South Wales. On the fifth fire-bombing circuit, at this location, the pilot filled the slung Bambi Bucket (bucket) without incident from a nearby dam and departed towards the fire area. Shortly after, the helicopter diverted off course, the bucket and longline became caught in trees and the helicopter collided with terrain. The pilot was fatally injured, and the helicopter was destroyed. The pilot’s post-mortem identified 2 heart conditions, one of which was coronary heart disease that was capable of causing sudden impairment and incapacitation.

ATSB investigation AO-2022-009

On 28 February 2022, the crews of 3 Robinson R44 helicopters were preparing to conduct crocodile egg collection in Arnhem Land, Northern Territory. The crews of 2 of the R44 helicopters collecting crocodile eggs nearby became concerned that they had not heard any communications from the crew of the third helicopter, which they reported was unusual. One of those helicopters returned to the area where they were last seen and found the fatally injured egg collector on the ground and the pilot, having sustained serious injuries, laying beside the helicopter that had collided with terrain. 

The pilot’s subsequent toxicology results detected 2 metabolites of cocaine. On the basis that the metabolites indicate exposure to cocaine, the detected levels indicated the pilot had not been exposed to cocaine within the previous 24 hours and may not have been affected by cocaine on the accident day. There was insufficient evidence to enable an assessment of whether the drug contributed to the development of the accident. However, the indication of exposure to cocaine is highlighted, as the effects of cocaine and post-cocaine exposure clearly increase risk to aviation activities. The post-cocaine exposure effects can include fatigue, depression and inattention.

ATSB investigation AO-2023-001

On 2 January 2023, the operator was conducting a series of scenic flights in 2 Eurocopter EC130B4 helicopters. The flights were performed under the visual flight rules from its base with the helicopters operating from separate helipads about 220 m apart. As one helicopter was preparing to land, the other helicopter took off. Shortly after, both helicopters collided. The landing helicopter was able to make a safe landing but the helicopter taking off crashed with the occupants being seriously or fatally injured.

The toxicology report for the fatally injured pilot showed a positive result for cocaine metabolites and the cutting agent levamisole. The ATSB’s interim investigation report found that, although it was unlikely the pilot would have had any psychomotor skill impairment on the day of the accident, it was not known whether post-cocaine exposure effects of the drug, which can include fatigue, depression and inattention, had any effect on the performance of the pilot.

Safety analysis

Introduction

On the afternoon of 6 October 2022, while flying at low level over Maitland Vale, New South Wales, a Bell 206B helicopter, registered VH-PHP, rolled markedly and descended rapidly, colliding with a riverbank. The helicopter was destroyed, and the pilot was fatally injured.

This analysis will consider the possible explanations for why the helicopter deviated from the pilot’s intended track and the final moments of the flight. It will also discuss the importance of disclosing medical information to CASA and the use of psychoactive drugs. 

Pilot incapacitation and collision with terrain

The pilot deviated from the defined VFR lane and flew for periods at low level before the helicopter departed controlled flight. The ATSB considered a number of possible reasons to explain these events.

Pilot manoeuvring

The manoeuvring performed when approaching Tocal and the subsequent deviation outside the VFR lane and flight at low level was unexpected given the pilot’s intention to track to Warnervale. At one point during the deviation, the helicopter slowed to 22 kt and descended to 120 ft above ground level, which could be interpreted as an approach to land, but the pilot then climbed away. It was also noted that the pilot did not respond to calls made by air traffic control. 

The pilot did not indicate to anyone their intention to deviate from the VFR lane and there was no known reason for the pilot to diverge from the track. To the contrary, the pilot stated to family by phone call just prior that the helicopter was flying well, and they would arrive at their destination in a short amount of time and that time would not have accommodated the deviation. The continued broadcasting by the pilot’s navigation software on their phone throughout the entire flight was evidence the pilot had a functional navigational aid.

Helicopter serviceability

While there were varying accounts by witnesses regarding the engine sound that could not be resolved and the helicopter had been in maintenance, the wreckage examination found no pre‑existing issues (mechanical or structural) that would have prevented normal operation. Numerous signatures of engine and driveshaft rotation were found indicating the powerplant and rotor system were functional. There were minimal signs of mast bumping, and the mast fractured in torsional overload indicating it failed on main rotor blade contact with the ground and the pilot did not excessively manoeuvre the helicopter.

Meteorological conditions

The weather forecast for the flight indicated some areas of low cloud and reduced visibility enroute, which could potentially explain the unexpected manoeuvring when near Tocal. However, an experienced pilot who was in the vicinity of the accident site reported the conditions as suitable for VFR operations. This was consistent with the meteorological equipment observations recorded at nearby Maitland Airport. Other witnesses near the VFR lane also reported weather consistent with these observations. Therefore, there was no evidence to indicate that the weather conditions directly contributed to the flight track deviation or the accident.

Pilot distraction

Distractions can occur unexpectedly, during any phase of flight, but when they have contributed to a safety occurrence, they have most often resulted in an incident rather than an accident (ATSB, 2006). There were no passengers on board, no other aircraft traffic was reported in the area at their altitude, and there was no evidence of any technical issues with the helicopter. While the pilot had been making phone calls, this was through the Bluetooth headset, which has simple handling. In addition, the flight time from Tocal and Vacy to the accident was 15 minutes and 5 minutes respectively, which should have been sufficient time to respond to the distraction and react appropriately. This included conducting a precautionary landing if the pilot had experienced a minor medical event. Therefore, a distraction event that was of sufficient magnitude and duration to result in the pilot losing awareness of their location and flightpath for this amount of time was considered to be unlikely. Further, distraction at the end of the flight was possible but considered unlikely due to the steep angle of pitch and bank prior to impact, which would not go unnoticed by an experienced pilot.

Pilot incapacitation

Pilot incapacitation is operationally defined as (International Civil Aviation Organization, 2012):

…any physiological or psychological state or situation that adversely affects performance.

Incapacitations can be divided into two operational classifications: “obvious” and “subtle”. Obvious incapacitations are those immediately apparent...onset can be “sudden” or “insidious” and complete loss of function can occur. Subtle incapacitations are frequently partial in nature and can be insidious because the affected pilot may look well and continue to operate but at a less than optimum level of performance. The pilot may not be aware of the problem or capable of rationally evaluating it.

ATSB research (ATSB, 2016) has shown that in-flight incapacitation can result from a variety of reasons, including changes in environmental conditions during the flight, the development of an acute medical condition, or the effects of a pre-existing medical condition. 

The air temperature at nearby Maitland Airport was not excessive. The pilot had finished a short phone call about 60 seconds before the accident. As such, it was unlikely the pilot had fallen asleep leading up to the accident, although it could not be discounted that this occurred immediately prior to the impact. Also, the pilot was reported to be experiencing a head cold from which they were recovering. However, this was unlikely to be a source of distress enough to not permit continued control of the helicopter. 

The pilot had notable changes in health during previous years including weight fluctuations, periods of high blood pressure and high cholesterol, insomnia, and lower back pain, for which the pilot had been prescribed various medications. 

In the 12 months prior to the accident, the pilot completed their aviation medical and was found to be below the baseline required for further cardiac assessment. Although, given the pilot’s medical history and job stressors, the designated aviation medical examiner (DAME) and pilot elected to conduct further cardiac testing. The assessment found only minor to moderate cardiac disease and that the pilot was at low risk of a significant cardiac event. 

However, the pilot’s post‑mortem examination found severe coronary atherosclerosis within all 3 major coronary arteries with at least 80% lumen stenosis observed. The ATSB’s aviation medical specialist noted that this could result in incapacitating chest pain leading to distraction and declining consciousness. This may possibly explain the unexpected deviation from the pilot’s intended track and the witness observations of the helicopter rolling markedly and descending rapidly before colliding with the riverbank. Nevertheless, it was not possible to forensically determine if the pilot experienced a heart attack prior to the accident. This is consistent with the ATSB research, which indicated it was likely that cardiovascular problems featured more prominently in general aviation accidents, but evidence of this was often difficult to establish with certainty, particularly in fatal accidents (ATSB, 2016). 

The pharmacological influence of the medication and controlled substances detected was assessed by a forensic pharmacologist and an aviation medical specialist. While the levels of diazepam and delta-9-tetrahydrocannabinol in the pilot’s blood sample were considered to result in some impairment of cognitive and psychomotor function, they were not at levels likely to exacerbate the pilot’s cardiac condition.

Despite this, in the absence of other reasonable scenarios to explain the unexpected events leading to the collision with terrain, the most plausible explanation was that the pilot likely experienced some level of incapacitation. However, the ATSB could not conclusively determine if this was due to a cardiac event, related to the medication and controlled substances, a combination of both, or for other unknown reasons.

Coronary artery disease

While a previous cardiac assessment identified the pilot had minor to moderate cardiac disease, the post-mortem found severe coronary atherosclerosis within all 3 major coronary arteries. With this level of disease, the ATSB’s aviation medical specialist advised that the pilot was at risk of a sudden incapacitating cardiac event. Similarly, the forensic pathologist also noted that the extent of the disease was a risk factor for sudden death. The post-mortem observations would suggest that the pilot’s cardiac disease had significantly increased in the period leading up to the accident.

Prior accidents and ATSB research have shown that, for fatal accidents with medical-related causes, coronary artery disease is one of the leading reasons for incapacitation, and for single‑pilot operations the majority leads to a fatal accident. Likewise, cardiovascular abnormalities were the most common incidental medical findings identified in pilot autopsies in the United States.

In this case, although it could not be determined if the pilot had experienced a heart attack, it remained a significant risk factor for the pilot. The initiation of a cardiac event can become so debilitating that the pilot becomes physically unable to control their own movements and thus the flightpath of the aircraft, which is particularly crucial in single-pilot operations.

Disclosure of medical information

As the holder of a pilot’s licence, the person is required to apply and obtain a medical certificate of an appropriate class if the person wishes to exercise the privileges of that licence. Aviation medical certificates have a period of validity, depending on their class, and need to be reapplied for at their expiry. As part of the medical process, the pilot is required to answer the DAME’s questions regarding their health and provide historical information so CASA can determine if the pilot meets the relevant medical standard. This includes the pilot completing a pre-medical questionnaire, which is reviewed by the DAME at the medical examination. 

The DAME was not aware of the medications the pilot had been prescribed as ongoing treatment for insomnia (Alprazolam and Amitriptyline hydrochloride), as they had not been declared by the pilot during their medical examinations. These 2 medications were classified by CASA as category D drugs, which would have made the pilot ineligible to receive an aviation medical certificate. The Alprazolam, which was found in the pilot’s blood sample, was a Therapeutic Goods Administration Schedule 8 controlled drug. 

The pilot also did not declare a spinal operation conducted 12 months before their last aviation medical examination, though the outcome of this was covered by a range of motion tests conducted by the DAME, which the pilot passed.

Medications and chronic conditions declared to a DAME permit medical conditions to be managed appropriately. Where an issue exists, alternative treatments and medications more compatible with aviation can be trialled, thereby permitting the pilot to manage both their own personal risks as well as those to aviation safety. A pilot should not exercise the privileges of their licence while taking a prohibited medication and should consult CASA or their DAME if they are unsure of a medication’s categorisation.

Psychoactive drugs and medications incompatible with aviation

The pilot’s blood sample contained psychoactive drugs, their metabolites and a cutting agent. In addition, the pilot had 2 medications determined by CASA to be incompatible with aviation safety. None of these drugs were permitted to be used in conjunction with flying.

The levels of diazepam detected were considered to be in the therapeutic range. 

The family reported that the pilot reported operations were normal during a phone call during the flight. Also, the pilot had been flying for about 2 hours without any apparent issues. Therefore, there was insufficient evidence to enable an assessment of whether the drugs and medications alone contributed to the accident. However, the forensic pharmacologist advised that some of these drugs were at levels where some impairment of the high-level psychomotor skills required for flying would be expected. In addition, at the levels detected for some of these drugs, there is a notable increase in risk-taking. 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the collision with terrain involving Bell Helicopter 206B, VH-PHP, 6.5 km east north-east of Maitland Airport, New South Wales on 6 October 2022. 

Contributing factors

  • While at low level, the pilot likely experienced an incapacitating event, leading to a collision with terrain.

Other factors that increased risk

  • The pilot had severe coronary artery disease, which is known to reduce the supply of blood to the heart muscle. This can cause chest pain, dizziness, shortness of breath and possible incapacitation.
  • The pilot did not disclose their use of prescription medicines to the Civil Aviation Safety Authority. This precluded specialist consideration and management of the ongoing flight safety risk the prescribed medications posed.
  • The presence of metabolites of controlled substances and prescription medications in the pilot's blood stream had the potential to affect their performance and ability to safely operate the helicopter.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • Coroner’s Court of NSW
  • NSW Police Service
  • NSW Forensic Medicine Service
  • Civil Aviation Safety Authority
  • the helicopter owner
  • the maintenance organisation for VH-PHP
  • Airservices Australia
  • OzRunways
  • Services Australia
  • Bureau of Meteorology
  • the pilot’s medical practitioners
  • the witnesses.

References

Australian Transport Safety Bureau. (2016). Pilot incapacitation occurrences 2010-2014 (AR‑2015-096). Retrieved from /publications/2015/ar-2015-096/

Australian Transport Safety Bureau. (2007). Analysis of Medical Conditions Affecting Pilots Involved in Accidents and Incidents: 1 January 1975 to 31 March 2006. Retrieved from https://www.atsb.gov.au/sites/default/files/media/32864/b20060170.pdf

Baselt, R (2001). Drug effects on Psychomotor Performance. Biomedical Publications, California. 

Baselt RC (2017). Disposition of toxic drugs and chemicals in man. 11th Edn. Biomedical Publications,California.

Bramness, J.G., Skurtveit, S. & Morland, J (2003). Testing the benzodiazepine inebriation-relationship between benzodiazepine concentration and simple clinical tests for impairment in a sample of drugged drivers. Eur. J. Pharmacol., 59:593-601.

Couper, F.J. & Logan, B.K. (2014 revision). Drugs and Human Performance Facts Sheets. Technical Report DOT HS 809 725, National Highway Traffic Safety Administration, Washington DC.

International Civil Aviation Organization. (2012). Doc 8984 Manual of Civil Aviation Medicine (3rd ed.). Retrieved from https://www.skybrary.aero/bookshelf/books/2242.pdf

Longo, M.C., Lokan, R.J. & White, J.M. (2001). The relationship between blood benzodiazepine concentration and vehicle crash culpability. J. Traffic Med., 29:36-43

Leufkens, T.R., Verneeren, A., Smink, B.E., van Ruitenbeek, P. & Ramaekers, J. G. (2007). Cognitive, psychomotor and actual driving performance in healthy volunteers after immediate and extended release formulations of alprazolam 1 mg. Psychopharmacology (Berl.), 191(4):951-959.

National Safety Council Committee on Alcohol and Other Drugs. (2012). Position on the Use of Cannabis (Marijuana) and driving. J. Anal. Toxicol., 37:47-49

Ricaurte E (2018) DOT/FAA/AM-18/8 Incidental Medical Findings in Autopsied U.S. Civil Aviation Pilots Involved in Fatal Accidents

Smink, B.E., Lusthof, K.J., de Gier, J.J., Uges, D.R.A. & Egberts, A.C.G. (2008). The relation between the blood benzodiazepine concentration and performance in suspected impaired drivers. J. Forensic & Legal Medicine, 15:483-488.

Verster, J.C., Volkerts, E.R. & Verbaten, M.N. (2002). Effects of alprazolam on driving ability, memory functioning and psychomotor performance: a randomized, placebo-controlled study. Neuropsychopharmacology 27(2): 260-269.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report. 

A draft of this report was provided to the following directly involved parties:

  • Civil Aviation Safety Authority
  • pilot’s medical practitioners
  • consultant pharmacologist
  • consultant aviation medical specialist.

Submissions were received from the Civil Aviation Safety Authority and a medical practitioner. The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2024

Title: Creative Commons BY - Description: Creative Commons BY

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to allow the pilot to see where the aircraft is going.

[2]     A VFR route is a designated track usually in an area of high-density traffic or restricted airspace to enable safe separation of VFR traffic. It is also referred to as a VFR lane.

[3]     These restricted zones cover from ground level to an altitude of 10,000 ft radially around Williamtown Airport and are used by military aircraft.

[4]     The pilot reportedly flew with a Bluetooth enabled aviation headset. 

[5]     The last position indicated on the track was the last reliable GPS fix. The OzRunways system reported 8 additional points, but these were discarded as being unreliable due to reflected signals.   

[6]     OzRunways is an electronic mobile application, utilising approved data for electronic maps, and used for navigation.

[7]     Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘scattered’ indicates that cloud is covering between a quarter and a half of the sky, ‘broken’ indicates that more than half to almost all the sky is covered, and ‘overcast’ indicates that all the sky is covered.

[8]     METAR: a routine report of meteorological conditions at an aerodrome. METAR are normally issued on the hour and half hour.

[9]     For VFR operations, when flying below the height of 3,000 ft above mean sea level or 1,000 ft above ground level (whichever is the higher) in Class G non-controlled airspace, a pilot is required to have 5,000 m flight visibility and to be clear of cloud. 

[10]    Mast bumping: abnormal contact between the main rotor hub and the rotor mast which, if excessive, could severely damage the mast, or result in the separation of the main rotor system from the helicopter.

[11]    A lumen is the inside space of a tubular structure, such as an artery or intestine.

[12]    Stenosis is the abnormal narrowing of a blood vessel or other tubular organ or structure.

[13]    Myocardial ischemia occurs when blood flow to the myocardium (the muscular tissue of the heart) is obstructed by a partial or complete blockage of a coronary artery by atherosclerosis.

[14]    Arrhythmia, or irregular heartbeat, is an abnormal rate or rhythm of the heartbeat. The heart may beat too quickly, too slowly, or with an irregular rhythm.

[15]    Myocardial infarction, colloquially known as ‘heart attack’, is caused by decreased or complete cessation of blood flow to a portion of the myocardium.

[16]    Atherosclerosis is the buildup of fats, cholesterol, and other substances in and on artery walls. This buildup is known as plaque. The plaque can cause arteries to effectively narrow, blocking blood flow.

[17]    Perivascular fibrosis is the increased amount of connective tissue in the heart vessels, which increases tissue stiffness.

[18]    A myocyte is a contractile cell (muscle cell).

[19]    Ventricular tachycardia is a type of irregular heart rhythm (arrhythmia) characterised by the lower heart chamber contracting poorly (quivering) but in a coordinated manner resulting in poor pumping function.

[20]    Ventricular fibrillation is a type of irregular heart rhythm (arrhythmia) characterised by the lower heart chamber contracting very rapidly but in an uncoordinated manner resulting in poor pumping function.

[21]    Diastolic blood pressure is how much pressure the blood is exerting against the artery walls while the heart muscle is resting between contractions.

[22]    Left ventricular hypertrophy is thickening of the walls of the lower left heart chamber.

[23]    Schedule 8 controlled drugs are substances that should be available for use but require restriction of manufacture, supply, distribution, possession and use to reduce abuse, misuse and physical or psychological dependence (Therapeutic Goods (Poisons Standard - October 2022) Instrument 2022).

[24]    Schedule 4 is for prescription only medicine. These are substances, the use or supply of which should be by or on the order of persons permitted by State or Territory legislation to prescribe and should be available from a pharmacist on prescription. However, some prescription medications have further specified controls applying to possession or supply. These are often referred to as restricted drugs or Schedule 4D medications (Therapeutic Goods (Poisons Standard - October 2022) Instrument 2022).

[26]    It should be noted that post-mortem blood samples are whole blood samples, but the reported therapeutic ‘blood’ concentrations from clinical studies are generally plasma concentrations. The blood/plasma ratio for diazepam is reported as being about 0.6 (Baselt 2017). Therefore, the reported blood concentration would be very conservative, and a plasma concentration would have been around 40% higher.

[27]    Aerodynamic stall: occurs when airflow separates from the wing’s upper surface and becomes turbulent. A stall occurs at high angles of attack, typically 16˚ to 18˚, and results in reduced lift and increased drag.

Preliminary report

Report release date: 17/11/2022

This preliminary report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

The occurrence

About 1350 local time on 6 October 2022, the pilot of a Bell 206 JetRanger helicopter, registered VH-PHP, departed Casino Airport, New South Wales for a ferry flight to Warnervale, New South Wales. The helicopter was in the process of being returned to its owner after a long‑term repair to correct hail damage and exchange life‑expired items. The pilot was the only person onboard. The aircraft tracked south-south-west, approximately 30-60 km inland of the coast (Figure 1).

Figure 1: VH-PHP flight track

Figure 1: VH-PHP flight track

Source: Google Earth and OzRunways, annotated by the ATSB

Recorded data indicated that at tracking point Wirradgurie, the pilot followed the inland visual flight rules (VFR) route west of Williamtown Airport through restricted areas R583B and R578E (Figure 2).[1] The VFR lane, designated D589B and D598A, is a 2-3 NM wide corridor under the restricted airspace from ground level to 2,500 ft above mean sea level (AMSL) and ground level to 1,600 ft AMSL, respectively. The VFR lane enables pilots to visually fly under the restricted airspace without requiring permission or monitoring by Williamtown airspace controllers. The VFR route follows the east coast rail line where it passes through the mountainous region between Gloucester and Maitland.

Figure 2: VH-PHP flight track through Williamtown VFR Route D589B and D589A

Figure 2: VH-PHP flight track through Williamtown VFR Route D589B and D589A

Source: Google Earth and OzRunways, annotated by the ATSB

At 1547 approaching Dungog, the pilot received a telephone call from a relative enquiring as to their progress. The pilot reported the aircraft was flying well, operations were normal, and they were 5 minutes from Maitland and 20 minutes from Warnervale.

Figure 3: VH-PHP flight track through Williamtown VFR Route D589A

Figure 3: VH-PHP flight track through Williamtown VFR Route D589A

Source: Google Earth and OzRunways, annotated by the ATSB

At 1556 approaching Tocal, approximately 4 NM from the end of the lane, the aircraft started to climb and then conducted a right 180° turn to backtrack northbound. After approximately 2 minutes the helicopter transitioned through the upper limit of the VFR lane and continued climbing to 3,100 ft. The helicopter then descended to 1,100 ft, back into D598A and continued to follow the lane northbound until Hilldale when the aircraft again made a right turn. This time the pilot flew outside the lateral bounds of the lane by conducting a gradual climbing orbit around a hill before crossing from the east to the west of the lane, reaching 2,900 ft during the transition.

The helicopter then descended over the town of Vacy, flying as low as 120 ft above ground level (AGL) before climbing and heading south. The aircraft then descended to low levels travelling parallel to, but just outside, the VFR lane western boundary until it exited the southern border of R578E at Maitland Vale.

At approximately 1616, the helicopter cleared a ridge by approximately 200 ft and descended gradually toward the Hunter River.

After clearing the ridge, the helicopter was observed by 6 witnesses. Common features of these reports were that the helicopter was heading towards the river, descending slightly, possibly initiating a turn when the helicopter rolled markedly and descended rapidly, colliding with the riverbank. The aircraft came to rest on a muddy river flat approximately 2 m from, and 0.5 m above, the water’s edge. The helicopter was destroyed, and the pilot was fatally injured.

Context

Helicopter information

The accident helicopter was a Bell 206 manufactured in 1970 as an 206A model. The helicopter was first registered in Australia in May 1986. In 1988, the helicopter was rebuilt and converted to a 206B model with fitment of a Rolls Royce/Allison 250-C20 turboshaft engine and the associated uprated transmission, rotor head and other changes.

A maintenance test flight associated with the replacement of components was conducted in Casino the day before the accident flight.

Site and wreckage examination

An initial assessment of the aircraft was conducted in situ after which, due to rising river levels, the wreckage was moved to higher ground and the principal components were moved to a secure location for further examination.

All major aircraft components were accounted for at the accident site. Examination of the aircraft’s flight controls, engine and aircraft structure did not identify any pre-existing defects. Fuel was found spilled at the accident site and fuel in the fuel filter bowl showed no evidence of contamination with water. Multiple sources of evidence indicating engine rotation at impact were identified.

The helicopter struck a tree on the riverbank, prior to impacting the ground. The tree and wreckage damage indicated the helicopter impacted the ground at approximately 80° right angle of bank and 60° nose down pitch.

Several aircraft components were retained by the ATSB for further detailed analysis.

Meteorological information

At 1600 the Bureau of Meteorology Meteorological Terminal Air Report (METAR)[2] for Maitland Airport reported 8 kt of wind with scattered cloud at 4,000 ft and 4,500 ft and overcast cloud at 7,800 ft above the airport.

Witnesses reported the weather at the time and location of the accident to be a mid to high level overcast cloud with no rain. A retired airline pilot reported that the ’Weather was suitable for VFR. A general base layer at 5,000 ft. Scattered cloud with patches to the South’.

Pilot qualifications

The pilot held a Commercial Pilot Licence (helicopter), a valid Class 1 Medical Certificate, a valid flight review, and a low-level helicopter rating.

Further investigation

To date, the ATSB has assessed the aircraft wreckage, interviewed witnesses and collected external data sources related to weather, air traffic communications, and flight tracking.

The investigation is continuing and will include further review and examination of:

  • aircraft maintenance documentation and operational records
  • recorded data
  • weather information
  • air traffic communications
  • pilot medical records, qualifications and experience.

Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

A final report will be released at the conclusion of the investigation.

Acknowledgements

The ATSB would like to acknowledge the accident site property owners and their extended family for the significant assistance they provided the ATSB with moving, handling and storage of the wreckage away from the rapidly rising floodwaters.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2022

CC BY logo

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1] These restricted zones cover from ground level to an altitude of 10,000 ft radially around Williamtown Airport and are used by military aircraft.

[2]     METAR: A meteorological report for an aerodrome at a routine time (half hourly) when conditions are better than specified thresholds

Occurrence summary

Investigation number AO-2022-048
Occurrence date 06/10/2022
Location 6.5 km east-north-east of Maitland Airport
State New South Wales
Report release date 25/06/2024
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Bell Helicopter Co
Model 206B
Registration VH-PHP
Serial number 607
Aircraft operator AUSTRALIAN NATIVE LANDSCAPES PTY LTD
Sector Helicopter
Operation type Private
Departure point Casino Airport, New South Wales
Destination Warnervale, New South Wales
Damage Destroyed

Birdstrike and collision with terrain involving Air Tractor AT-502B, VH-KDR, 32 km east-north-east of Chinchilla Airport, Queensland, on 19 September 2022

Final report

Report release date: 28/06/2023

Executive summary

What happened

On the morning of 19 September 2022, the pilot of an Air Tractor AT-502B aircraft, registered VH‑KDR and operated by Smart Air Services, was completing aerial spray operations near Chinchilla, Queensland. After becoming concerned at not being able to contact the pilot, the spray company alerted nearby farmers to assist, and the aircraft was subsequently found in the paddock being sprayed. The pilot was fatally injured and the aircraft was destroyed.

What the ATSB found

The ATSB found that, while the pilot was conducting a spray run parallel to the paddock fence line at about 8 ft above the ground, a large bird (Australian bustard) struck the right Perspex windshield. During the impact, the right windshield was shattered, with the bird carcass found inside the aircraft.

The site examination showed that, after the birdstrike, the aircraft continued flying for a further 310 m, or about 5 seconds. However, without any flight data, it could not be exactly determined what occurred during this time. Despite this, the ATSB established that, it was likely that the birdstrike affected the pilot’s ability to control the aircraft, resulting in a collision with terrain.

Safety message

Birdstrikes are relatively common with over 1,300 occurrences reported to the ATSB in 2022. While these strikes typically result in nil-to-minor damage to an aircraft and nil-to-minor injuries to occupants, there have now been 2 confirmed fatal accidents in Australia. This accident highlights the ongoing hazards of birdstrikes to aircraft, particularly during low-level spraying operations.

Where applicable, there are published recommended practices available from the Australian Aviation Wildlife Hazard Group (2014) to manage risk of wildlife strikes for organisations that may be involved in a wildlife strike occurrence. Practices include considering the likelihood of a wildlife strike and proximity of known wildlife to aircraft manoeuvring areas and flight paths, as well as identifying wildlife characteristics such as their agility, speed, manoeuvrability, and their ability to avoid aircraft. Other considerations include the consequence of a strike, including the effects of the mass of the wildlife species, the velocity of the aircraft involved, the resultant impact force(s) and the damage that could result; and if adequate control of the aircraft can be maintained following a strike event. If a birdstrike does occur, available protections for a pilot include the wearing of flight helmets, 4‑point seatbelts, and the fitment of thicker aircraft windshields, where possible.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On the morning of 19 September 2022, the pilot of an Air Tractor AT-502B aircraft, registered VH‑KDR and operated by Smart Air Services, was conducting aerial spray operations on a property near Chinchilla, Queensland. The operations base for the day was at a private airstrip south-east of Chinchilla, where the aircraft was to be loaded with fungicide, pesticide, and fuel. The 2 farms to be sprayed were located several kilometres to the north of the airstrip (Figure 1).

Figure 1: Location of the airstrip and area of operations

Figure 1: Location of the airstrip and area of operations

Source: Google Earth, annotated by the ATSB

Numerous spray runs were completed on the paddocks during the morning between 0704 and 1012 local time, with the pilot returning to the airstrip on 4 occasions to reload the spray chemicals and to refuel the aircraft. Recorded GPS data from the aircraft’s Satloc[1] system identified that, at 1058, the pilot departed the airstrip to continue herbicide spraying on the northerly paddock. By 1125, the pilot had completed 17 spray runs within the paddock in a racetrack pattern (Figure 2).

At the conclusion of run 17, the aircraft was turned onto a northerly heading, flown parallel to the fence line, before being turned onto a reciprocal heading to spray this area (Figure 2). The final GPS data point recorded by the Satloc system was at 11:25:41, 3 seconds after the pilot had commenced the southerly fence line spray run.

After 1200, the loader at the airstrip attempted to phone the pilot to ask whether more fuel was required, however, no response was received. The loader was concerned at not being able to contact the pilot, and phoned the company operations manager, who then contacted nearby farmers to assist with locating the aircraft. At about 1215, a local farmer found the aircraft wreckage in the paddock where the pilot had been spraying. The pilot was fatally injured and the aircraft was destroyed.

Figure 2: Accident site and spray runs (orange)

Figure 2: Accident site and spray runs (orange)

Source: SatLoc data provided by the aircraft operator overlaid on Google Earth, annotated by the ATSB

Context

Pilot information

The pilot held a valid Class 1 Aviation Medical Certificate and a Commercial Pilot Licence (Aeroplane). The pilot also held aerial application and low-level ratings, as well as tailwheel and retractable undercarriage, manual propellor pitch control, and turbine engine endorsements.

The pilot had accumulated 3,738 hours of aeronautical experience, of which 2,681 hours was in turbine agricultural aircraft.

Aircraft information

General information

VH-KDR was an Air Tractor Incorporated 502B single-seat low-wing tailwheel aircraft manufactured in the United States in 1996. It had a total wingspan of 15.8 m and was powered by a Pratt & Whitney Canada PT6A‑34AG turboprop engine. It was first registered in Australia on 6 August 2004. It was issued with a Special Certificate of Airworthiness in therestricted category[2] on 10 August 2004. A maintenance release was issued on 9 September 2022.

Windshield information

The Air Tractor 502B windshield is constructed of 3 pieces being either glass or Perspex (Figure 3). The centre windshield is manufactured from glass. The thickness of the glass on VH‑KDR was 1/4-inch, which was the standard thickness when the aircraft was manufactured. The 2 side pieces were manufactured from Perspex.

Figure 3: Air Tractor AT-502B windshield


Figure 3: Air Tractor AT-502B windshield

Source: Storm Aeronautics

The ATSB contacted Air Tractor regarding the availability of thicker side windshields and they advised that there had been no consideration for using thicker material. The manufacturer stated that the windshield design on the Air Tractor is standard for the agricultural aviation industry, and in previously reported birdstrikes where the bird had entered the aircraft through either side windscreen, the bird missed the pilot and hit the back wall. Further, they described difficulties in replacing the Perspex windshield with glass due to the curvature of the design, which would increase the likelihood of glare and would add weight.

In 2009, Air Tractor issued a service letter advising that thicker centre windshields were being installed in current production aircraft. The thicker windshields were 3/8-inch thick glass compared to the original 1/4-inch. The letter also advised that the thicker windshields could be installed in existing aircraft, though not mandatory. This letter was issued after operators had reported on birdstrikes that had resulted in the bird carcass entering the cockpit through the centre windshield (refer to section titled Related occurrences).

Meteorological information

Based on information recorded from a private weather station located in the paddock being sprayed, the air temperature around the time of the accident was 26.3 °C, and the average wind speed was about 9 kt from the west-south-west. The calculated crosswind component was about 8 kt.

Wreckage and impact information

The ATSB’s on-site examination found that the aircraft had impacted the ground, adjacent to the fence line. The aircraft’s orientation was consistent with the direction of travel. The left wing had initially impacted the ground, followed by the fuselage, in a near vertical attitude. The propeller and engine were buried in the soft earth, with the spread of wreckage contained to a small area. Ground scars and damage to the left wing indicated that the wing struck the ground at about 30° to the horizontal (Figure 4). The length of the ground scar from the point of impact to the fuselage was about 12.6 m.

Figure 4: Aircraft wreckage at the accident site

​ not being able to contact the pilot, the spray company alerted nearby farmers to assist, and the aircraft was subsequently found in the paddock being sprayed. The pilot was fatally injured and the aircraft was destroyed.  What the ATSB found The ATSB found that, while the pilot was conducting a spray run parallel to the paddock fence line at about 8 ft above the ground, a large bird (Australian bustard) struck the right Perspex windshield. During the impact, the right windshield was shattered, with the bi

Source: ATSB

Examination of the wreckage identified that:

  • Inspection of the propeller and engine indicated the engine was delivering power at the time of the impact.
  • Fuel and chemical product residues were also found at the accident site.
  • There was no post-impact fire.
  • Due to the extent of damage to the cockpit in the accident sequence, it was not possible to determine the position of the engine controls prior to the impact. However, where possible, control continuity was established.
  • It was very likely the aircraft was trimmed ‘nose-up,’[3] which was reported by the operator to be the configuration[4] typically used when conducting low-level aerial spraying.
  • There were no pre-existing technical failures with the aircraft that would have contributed to the accident.

A large bird carcass was found in the cockpit and severed bird wings were located about 310 m north of the wreckage, in-line with the aircraft’s track along the fence line, which indicated the approximate location of the initial birdstrike (Figure 5). Bird feathers were found along flight path in between location of wings and aircraft wreckage. Biological residue from the bird was found outside the right cockpit window and among the pieces of Perspex from that window. Further biological residue was found on the left side of the cockpit behind the pilot’s seat, indicating the bird passed through the right cockpit window in an upward trajectory towards the left side. There was no evidence of the bird striking any other part of the aircraft.

Figure 5: Site map with key locations

Figure 5: Site map with key locations

Source: Google Earth, annotated by the ATSB

Recorded data

The SatLoc data’s final recorded point was about 800 m north of the wreckage, and 500 m from the location of the severed bird wings (Figure 2). Based on the aircraft's previously recorded ground speed and direction of travel, there were about 5 seconds between the birdstrike occurring and the impact with the ground. The ground speed of the aircraft was about 116 kt (200 km/h), which was a similar speed to other runs, and the height was about 8 ft above ground level,[5] which was a similar height to the previous runs.

Medical and pathological information

The post-mortem report indicated that the pilot did not have any pre-existing medical conditions nor consumed any substances likely to have contributed to the accident. The report indicated that the pilot sustained significant head injuries in the accident. It was also noted that feathers were found on the pilot’s neck and chest, but it could not be determined whether they were the direct result of the birdstrike or from the accident sequence. Therefore, it was unknown whether these injuries sustained were due to the birdstrike or collision with terrain, or both.

Bird identification

Recovered biological specimens of the bird, including wing feathers and residue from the carcass, were analysed by the Australian Centre for Wildlife Genomics at the Australian Museum. The specimens were identified as a Ardeotis australis, commonly known as an Australian bustard (or bush/wild/plains turkey) (Australian Museum 2020).

The Australian bustard is a large bird, 80 to 120 cm in length and a wingspan of up to 230 cm (Ziembicki 2010). An average adult bird weighs 4.5 kg, however, males can weigh up to 8 kg (Bird Fact 2022). Australian bustards are capable of flying but are mostly ground dwelling. They are Australia’s heaviest flying bird. The bird carcass recovered had a wingspan of at least 120 cm and a length of 100 cm; the gender was unknown.

Survival aspects

First responders to the accident site identified that the pilot had been fastened into the seat by the aircraft’s 4‑point restraint harness. A flight helmet was found within the wreckage, which the pilot had been wearing, but it had become dislodged and sustained damage to the right-side shell and left‑side earpiece during the accident sequence. The left-side helmet strap had separated from the earpiece. Yellow paint transfer from the rear of the cockpit was found on the back of the helmet. Bird biological residue was found on the inner surface of the helmet visor.

Severe compression of the forward fuselage and cockpit region had occurred as a result ground impact forces. The accident was not considered survivable.

Related occurrences

Birdstrikes are a recognised hazard in aviation and there are mitigators in place around airports, however, there are challenges when operating outside of these areas. A review of Australian and international data and investigation reports found the following occurrences involving birdstrikes during aerial spraying operations.

Australian data

A review of the ATSB occurrence database from 2000 to 2022 found that 30 birdstrike occurrences were reported during aerial spraying operations. Of those, one resulted in minor injury, 20 resulted in minor damage, and one resulted in substantial damage. For example:

  • On 4 February 2000, the pilot of an Air Tractor 502B was conducting aerial spraying operations 15 km west of Moree, New South Wales. As the aircraft approached the start of a spray run at approximately 50 ft above ground level, a large bird struck the front windshield. The pilot sustained minor injuries and the aircraft sustained minor damage.
  • On 9 November 2011, an Air Tractor 802A struck an Australian bustard while conducting aerial spraying operations, 37 km south-east of Emerald Airport, Queensland. The impact damaged the wing, resulting in a loss of control and the aircraft sustained substantial damage. The pilot was uninjured.

In 2022, there were 2 fatal accidents involving birdstrikes, including this accident. The other accident was a private helicopter flight, investigated as AO-2022-034. This was the only fatal birdstrike confirmed in Australia.

United States data

A review of the United States Federal Aviation Administration wildlife strike database identified 2 birdstrikes resulting in damage to the windshield while conducting aerial spraying operations:

  • On 15 April 2000, the pilot of an Air Tractor 502B reported that a red-tailed hawk struck and damaged the windshield during a spray run near Prescott, Washington, resulting in minor injuries.
  • On 9 June 2017, the pilot of an Air Tractor 502B reported a birdstrike occurring while conducting spraying operations about 10 miles west of Salt Lake City Airport, Utah. The birdstrike damaged the right front window, which resulted in the door opening. The pilot was uninjured and conducted a precautionary landing. The bird species was unknown.

In addition, Air Tractor reported another 3 instances involving birdstrikes resulting in minor windshield damage and nil injuries:

  • On 30 October 2015, an Air Tractor AT-402B struck a bird during mosquito control activity.
  • On 24 August 2020, while returning from a drop during firebombing operations, the windshield of an Air Tractor AT-802A broke due to a birdstrike.
  • On 24 October 2021, an ibis entered the cockpit through the windshield of an Air Tractor AT‑802.
South African data

On 11 September 2008, the pilot of an Air Tractor 502B was conducting aerial spraying operations on a farm in the Caledon region of South Africa. During a spray run, a witness on the ground, who was approximately 700 m from the aircraft heard an aircraft noise and immediately after, an explosion. The aircraft wreckage was located in a field in an inverted position. The pilot was fatally injured.

Bird remains and feathers were identified inside the aircraft cockpit. A piece of glass windshield was also found within the cockpit that was covered in bird remains. The carcass of a blue crane was found near the wreckage. The investigation was unable to determine if the pilot was incapacitated or fatally injured as a result of the collision with the bird before the impact with the ground.

As a result of the investigation, the South African Civil Aviation Authority (investigation CA 18/2/3/8548) made the following recommendation:

Request the Air Tractor manufacturer to investigate the possibility of replacing the existing windshield with a thicker, stronger windshield to be used by clients operating these aircraft in areas of high bird activity.

The following year, Air Tractor published a service letter with details of a new, thicker windshield available to be fitted (refer to section titled Windshield information).

Safety analysis

Birdstrike and resulting collision with terrain

The location and impact point of the aircraft wreckage was consistent with the previously recorded flight path. Further, the presence of the Australian bustard carcass inside the aircraft wreckage, and the identification of the bird’s wings around 310 m north of the wreckage, indicated that the aircraft had experienced a birdstrike while flying the southbound spraying track at about 8 ft above ground level.

Considering the recorded ground speed of the aircraft on the 17 previous spray runs and up to the last recorded data point, it was likely that the aircraft struck the bird while flying at about 116 kt (200 km/h). This resulted in a collision with sufficient energy to break the right Perspex windshield as evidenced by the biological residue found on the aircraft and broken windshield pieces.

Given the expected track and speed of the aircraft, and the location of the bird wings to the wreckage, the aircraft sustained flight for about 5 seconds following the birdstrike. As the aircraft was operating around 8 ft above ground level, and the wingspan (total of 15.8 m) was longer than this height, it was likely the aircraft entered a short climb to result in a near vertical attitude at impact, indicative of a loss of control. There was also significant damage to the pilot’s helmet as well as a small amount of bird biological residue found in the visor. However, in that time, the ATSB could not determine exactly what occurred as a result of the bird entering the aircraft as no flight data was recorded nor was the extent of the pilot’s injuries from the birdstrike known. That is, whether the pilot sustained a level of incapacitation due to a direct strike from the bird, or whether they experienced a level of startle or distraction following the event.

Therefore, with no other reasonable explanation and having excluded a pre-existing medical condition, it was likely that the birdstrike affected the pilot’s ability to control the aircraft when operating at low-level, resulting in a loss of control and collision with terrain.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the birdstrike and collision with terrain involving Air Tractor 502B, VH-KDR, on 19 September 2022.

Contributing factor
  • During aerial spraying operations at low-level, a large bird (Australian bustard) struck the right windshield of the aircraft and entered the cockpit. This likely affected the pilot’s ability to control the aircraft, resulting in a collision with terrain.

Sources and submissions

Sources of information

Sources of information during the investigation were gathered from:

  • Smart Air Services Pty Ltd
  • the aircraft loader
  • Air Tractor Incorporated
  • Pratt & Whitney Canada
  • Civil Aviation Safety Authority
  • maintenance organisation for VH-KDR
  • Queensland Police Service.

References

Australian Museum (2020) Australian Bustard. Retrieved from https://australian.museum/learn/animals/birds/australian-bustard/

Bird Fact (2022) Australian Bustard - Ardeotis australis. Retrieved from https://birdfact.com/birds/australian-bustard

Ziembicki, M (2010) Australian Bustard. CSIRO Publishing: Collingwood.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the following directly involved parties:

  • Smart Air Services Pty Ltd
  • the aircraft loader
  • Air Tractor Incorporated
  • Pratt & Whitney Canada
  • Civil Aviation Safety Authority
  • Transportation Safety Board of Canada
  • United States National Transportation Safety Board.

Submissions were received from Air Tractor Incorporated. The submission was reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2023

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Satloc: an aerial guidance system that provides the pilot with guidance commands to fly accurate spray patterns.

[2]     Restricted category aircraft are limited to operate and carry personnel only for specified purpose/s.

[3]     The elevator trim control lever was found to be in the ‘nose-up’ position. However, the left elevator trim tab was found to be in the ‘up’ position, which would be consistent with the control lever in the ‘nose-down’ position. This discrepancy likely resulted from compression of the fuselage due to the impact with terrain. This was based on the rod connecting the controls to the trim tab likely sliding towards the rear of the aircraft while the fuselage compressed, moving the trim tab ‘up’ or in the ‘nose-down’. Therefore, it was likely that the aircraft was trimmed nose-up prior to the accident.

[4]     If forward pressure was removed from the yoke, the aircraft would climb for safety reasons.

[5]     The data was adjusted based on the location of the SatLoc antenna and the spray broom as there was approximately 8 ft between these points.

Preliminary report

Report release date: 16/12/2022

This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

The occurrence

On 19 September 2022, the pilot of an Air Tractor AT-502B aircraft, registered VH-KDR and operated by Smart Air Services, was conducting spraying operations on a property near Chinchilla, Queensland.

At about 0704 Eastern Standard Time,[1] the aircraft departed from a private airstrip 24 NM (44 km) south-east of Chinchilla, with the first load of fungicide. Recorded GPS data from the aircraft’s Satloc system showed that, by 0900, the pilot had sprayed 2 loads on that property. The aircraft was then refuelled and the chemical hopper reloaded at the airstrip.

The pilot then sprayed 2 loads of pesticide (the third and fourth loads of the day) on a different paddock, before returning to the airstrip. The aircraft’s hopper was then reloaded before departing with the fifth load to continue spraying the same paddock (Figure 1).

Figure 1: Location of the airstrip and spray paddock

Figure 1: Location of the airstrip and spray paddock

Source: Google Earth, annotated by the ATSB

After completing 17 spray runs on the paddock in a racetrack pattern, at about 1125, the aircraft was turned to track north along the western boundary (Figure 2). The aircraft was then turned at the northern end to commence the 18th spray run to the south. The last GPS data point was recorded 3 seconds after starting this run.

After 1200, the loader attempted to call the pilot to ask whether they needed more fuel but received no response. The loader was concerned having received no response, and phoned the operations manager, who contacted nearby farmers to assist with locating the aircraft. At about 1215, a local farmer found the aircraft in the paddock where the pilot had been spraying. The pilot was fatally injured, and the aircraft was destroyed.

Figure 2: Accident site and spray runs (orange)

Figure 2: Accident site and spray runs (orange)

Source: Satloc data provided by the aircraft operator overlaid on Google Earth, annotated by the ATSB

Context

Pilot information

The pilot held a valid Class 1 Aviation Medical Certificate and a Commercial Pilot Licence (Aeroplane). The pilot also held aerial application and low-level ratings, as well as tailwheel and retractable undercarriage, manual propellor pitch control, and turbine engine endorsements.

The pilot had 3,738 hours of aeronautical experience, of which 2,681 hours was in turbine agricultural aircraft.

Meteorological information

Based on information from a private weather station located in the paddock being sprayed, around the time of the accident, the air temperature was 26.3 °C, and average wind speed was about 9 kt from the west-south-west.

Operational information

The operator advised that they expected that accident run field would be sprayed at a height of about 2 m (6 ft) above the ground, to be just above the weeds.

The Satloc GPS data indicated the aircraft had a ground speed of 116 kt for the accident spray run.

Site and wreckage information

The ATSB’s site examination found that the aircraft had impacted terrain with the fuselage in a near vertical attitude. The propeller and engine were buried in the soft earth, with the wreckage contained to a small area. Ground scars and damage to the left wing indicated that the wing struck the ground at about 30° to the horizontal (Figure 3).

Figure 3: Aircraft wreckage and exemplar aircraft (inset)

Figure 3: Aircraft wreckage and exemplar aircraft (inset)

Source: ATSB and Air Tractor (inset), annotated by the ATSB

Examination of the propeller and engine indicated that the engine was delivering power at the time of the impact. Fuel and chemical product residues were also found at the accident site, but there was no post-impact fire.

A large bird carcass was found in the cockpit and the bird’s wings were located about 300 m north of the wreckage, in-line with the aircraft’s track. Biological residue from the bird was found outside the right cockpit window.

Bird identification

Recovered biological specimens of the bird, including the feathers from the wing and residue from the carcass, were analysed by the Australian Centre for Wildlife Genomics at the Australian Museum. The specimens were identified as a Ardeotis australis, commonly known as an Australian bustard or Plains turkey.

The Australian bustard is a large bird, 80 to 120 cm in height, with an average weight for an adult of 4.5 kg, with males weighing up to 8 kg. They are capable of flying but are mostly ground dwelling.

Further investigation

The investigation is continuing and will include further review and examination of:

  • electronic components recovered from the accident site.
  • operational documentation.
  • maintenance records.
  • research and similar occurrences.

Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

A final report will be released at the conclusion of the investigation.

Acknowledgements

The ATSB acknowledges the support of the local farmers and Queensland Police Service for their assistance during the on-site investigation.

References

Australian Museum (2020). Australian Bustard. https://australian.museum/learn/animals/birds/australian-bustard/

Bird Fact (2022). Australian Bustard - Ardeotis australis. https://birdfact.com/birds/australian-bustard

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2022

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Eastern Standard Time (EST): Coordinated Universal Time (UTC) + 10 hours.

Occurrence summary

Investigation number AO-2022-043
Occurrence date 19/09/2022
Location 32.3 km east-north-east of Chinchilla Airport
State Queensland
Report release date 28/06/2023
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Birdstrike
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Air Tractor Inc
Model AT-502B
Registration VH-KDR
Serial number 502B-0361
Aircraft operator SMART AIR SERVICES PTY LTD
Sector Turboprop
Operation type General Aviation
Departure point Walugra Airstrip, Queensland
Destination Walugra Airstrip, Queensland
Damage Destroyed

Collision with terrain involving Robinson R22 Beta, VH-CWE, Budgerygar Station, Queensland, on 26 September 2022

Discontinuation notice

Report release date: 24/01/2023

Section 21 (2) of the Transport Safety Investigation Act 2003 (TSI Act) empowers the ATSB to discontinue an investigation into a transport safety matter at any time. Section 21 (3) of the TSI Act requires the ATSB to publish a statement setting out the reasons for discontinuing an investigation. The statement is published as a report in accordance with section 25 of the TSI Act, capturing information from the investigation up to the time of discontinuance.

Overview of the investigation

On 27 September 2022, the ATSB commenced an investigation following notification of a collision with terrain involving a Robinson R22 Beta helicopter, registered VH-CWE.

About 1300 local time, on 26 September 2022, the helicopter departed a rural property, with the pilot and one passenger on board, reportedly to perform a weed inspection of that property. While flying at low altitude, the pilot lost control of the aircraft and collided with terrain. The aircraft was substantially damaged, with the pilot sustaining serious injuries, and the passenger receiving minor injuries.

The ATSB evaluated photographic evidence of the wreckage and interviewed the pilot and witnesses. There were no reported problems with the helicopter prior to the collision with terrain. The first items in the wreckage trail were the landing gear, which had separated from the helicopter and had contact marks consistent with impact to the left struts. The main wreckage was located about 400 m away on its side adjacent to the road with no obvious pre‑accident defects (Figure 1 and Figure 2).

Based on the available evidence it is likely that the accident was due to a handling error while operating at low level. 

A review of Civil Aviation Safety Authority (CASA) licencing information identified that the pilot held both Commercial and Private Pilot Licences (Helicopter) and a low-level mustering endorsement. However, they did not hold a current medical certificate and CASA had no evidence that the pilot had conducted a flight review within the required period to enable operation of the R22 helicopter. As such, they were not entitled to exercise the privileges of their licence at the time of the accident.

Figure 1: Landing gear assembly components and final helicopter location

Figure 1: Landing gear assembly components and final helicopter location

Source: Queensland Police, annotated by the ATSB

Figure 2: Helicopter wreckage

Figure 2: Helicopter wreckage

Source: Queensland Police

Reasons for the discontinuation

Based on a review of the available evidence, the ATSB considered it was unlikely that further investigation would identify any systemic safety issues or important safety lessons. Consequently, the ATSB has discontinued this investigation.

The evidence collected during this investigation remains available to be used in future investigations or safety studies. The ATSB will also monitor for any similar occurrences that may indicate a need to undertake a further safety investigation.

Occurrence summary

Investigation number AO-2022-044
Occurrence date 26/09/2022
Location Budgerygar Station
State Queensland
Report release date 24/01/2023
Report status Discontinued
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Discontinued
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Serious

Aircraft details

Manufacturer Robinson Helicopter Co
Model R22 BETA
Registration VH-CWE
Serial number 4522
Sector Helicopter
Damage Substantial

Ground strike involving Ayres Corporation S2R-T15, VH-IWI, Trangie, New South Wales, on 31 August 2022

Final report

Report release date: 06/04/2023

Executive summary

What happened

On 31 August 2022, an Ayres Corporation S2R-T15, registered VH-IWI, was conducting aerial application operations. Around 100 m into a take-off roll, the pilot heard a bang as the left wing hit the ground and the aircraft performed a ground loop. No injuries were sustained.

Inspection revealed that the left main landing gear shock assembly had failed, with the left main landing gear folding outwards and contacting the bottom of the wing.

What the ATSB found

The ATSB examination identified that the lower tube of the left shock strut assembly failed at a fatigue crack, which led to the collapse of the left main landing gear and the aircraft wing to strike the ground. It is very likely that this lower tube was a part that Thrush Aircraft had instructed owner/operators to replace or modify in 1994 in accordance with a service bulletin. The reason the part was not replaced or modified was not identified.

Safety message

Manufacturers issue service bulletins to inform owners and operators about critical and useful information on aircraft safety, maintenance, or product improvement. The ATSB strongly encourages compliance with service bulletins pertaining to aircraft safety.

Additionally, on acquisition of an aircraft, it is important to review maintenance documentation to determine whether all the appropriate manufacturer issued instructions have been addressed.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 31 August 2022, an Ayres Corporation S2R-T15, registered VH-IWI, was conducting aerial application operations from Trangie Airport. The pilot was the only person on board.

Three application flights were scheduled for the day, and after performing the daily aircraft inspection, the pilot commenced the first flight at around 0800 local time. Once the first flight was complete, the pilot obtained fuel and chemical, and taxied back to the airstrip to commence the second flight. The aircraft was around 100 m into the take-off roll when the left wing struck the ground, resulting in the pilot’s view being obstructed with chemical, and the aircraft started to rotate. In an attempt to stop the aircraft, the pilot applied reverse thrust. After completing a ground loop, the aircraft came to rest near the left edge of the runway. No injuries were sustained.

Initial inspection revealed that the left main landing gear shock assembly had failed, with the left main landing gear folding outwards and contacting the bottom of the wing.
 

Context

Operational and maintenance history

VH-IWI was manufactured by the Ayres Corporation in 1980 and first registered in Australia on the 24 December that year. The aircraft was powered by a Pratt & Whitney PT6A -15AG engine. It had accumulated 14,474.5 hours total time in service. The last maintenance took place 2 days prior to the occurrence and the right landing gear was replaced in 2012.

The Ayres Corporation[1] had issued 2 service bulletins associated with the main landing gear shock strut assembly.[2] The first, SB-AG-31,[3] was issued in 1992 in response to failures that occurred in the upper tube. This service bulletin described a modification to strengthen the upper tube, adding 4 rosette welds to the existing 2 rosette welds.[4] An entry in the aircraft maintenance logbook indicated that shock struts were welded to comply with SB-AG-31.

The second service bulletin, SB-AG-36,[5] was issued in 1994 in response to failures that occurred in the lower tube and included strengthening the lower tube. SB-AG-36 described 5 methods to comply with the bulletin:

  • (1) replace shock assembly with P/N 50116-29 (new)
  • (2) replace shock assembly with P/N 50116-28F1 (re-worked)
  • (3) replace lower tube P/N 50116-12 with P/N 50116-12F (modified)
  • (4) replace lower tube P/N 50116-12 with P/N 50116-30 (new design)    
  • (5) modify old lower tube P/N 50116-12

Option (5) described the removal of a plug from the top of the tube, removal of a 0.12” (3.0 mm) thick and 1 3/8” (34.9 mm) long reinforcing tube, insertion and welding (including rosette welds) of a 0.312” (7.9 mm) thick and 4.25” (108.0 mm) long reinforcing tube P/N 50116-100, and attachment of a plug by welding. No logbook record indicating compliance with SB-AG-36 was found. The current maintainer stated they were performing maintenance under the assumption that all previous maintenance had been performed according to the manufacturer’s instructions. The reason the lower tube was not replaced or modified when the service bulletin was issued was not identified.

The operator of VH-IWI acquired the aircraft in 2018. The maintainer commenced maintaining the aircraft in the 12 months leading up to the occurrence. They were not the maintainer of the aircraft when either SB-AG-31 or SB-AG-36 were issued.

ATSB technical examination

Examination of the damaged main landing gear shock strut assembly was conducted at the ATSB’s technical facilities. The overall condition of the assembly was aged, and the rubber shock biscuits were cracked (Figure 1).

Figure 1: Left main landing gear shock strut assembly

Figure 1: Left main landing gear shock strut assembly

Schematic and photo showing the main landing gear shock struct assembly with components labelled. The assembly was dirty and the shock biscuit exhibited cracks.

Source: Thrush Aircraft (schematic), ATSB (photo and annotations)

The grease between the upper and lower tube was discoloured; however, there was fresh blue grease around the lubricator and within the lower tube near the point of fracture. A substantial amount of new grease appeared to have migrated out of the lower tube during the occurrence.

The left shock strut fractured at the hole where the lower steel tube attached to the slider plate
(Figure 1). This allowed the bottom portion of the lower tube to separate from the remaining shock assembly. The fracture was consistent with fatigue cracking, followed by unstable crack growth and ductile overstress (Figure 2).

Figure 2: Fractured lower tube exhibiting characteristics of fatigue fracture followed by overstress

Figure 2: Fractured lower tube exhibiting characteristics of fatigue fracture followed by overstress

Fracture surface exhibiting characteristic of fatigue cracking followed by overstress.

Source: ATSB

The construction of the fractured lower tube consisted of a steel tube, around 3 mm thick and 400 mm long, reinforced inside with a smaller diameter section of tube, around 3mm thick and 35 mm long, over the region of the through-hole. The reinforcing tube was welded to the lower tube at the top end. There was no end cap on the lower tube, which was present on a more recently-manufactured lower tube. There were no rosette welds connecting the lower tube and the reinforcing tube. The upper tube of the left shock strut assembly was also examined; there were 6 rosette welds present on the upper tube.

There was a handwritten marking on the side of the lower tube (Figure 3) which was identified as the characters ‘50116T012 25[?]’, with an indistinct character at the end.

Figure 3: Marker writing on the lower tube

Figure 3: Marker writing on the lower tube

Writing on the lower tube written in black marker. The characters are 50116T012 25[?].

Source: ATSB

Advice from Thrush Aircraft

When asked about the writing on lower tube Thrush Aircraft informed the ATSB that first 5 characters represented a drawing number,[6] the 3 numbers to the right of the ‘T’ identified the component on that drawing. The drawing number, together with the component identifier, was considered the ‘part number’ and these numbers, 50116-012, were consistent with the designation of the pre-1994 lower tube design. Thrush Aircraft suggested the final 3 digits might be an employee or serial number.

A representative from Thrush Aircraft concluded that, based on the available evidence, the failure was consistent with the failures that prompted SB-AG-36.

Safety analysis

The ATSB examination identified that the lower tube of the left shock strut assembly failed at a fatigue crack. The crack had initiated from the hole where the lower tube attached to the slider plate and propagated around the circumference of the tube. The final fracture most likely took place early in the take-off roll which led to the collapse of the left landing gear and the aircraft wing striking the ground.

The dimensions of the reinforcing tube[7] and the writing on the side of the part were most consistent with the original part, noting that there was no plug. This part was to be replaced or modified to comply with SB-AG-36. It was not possible to determine the exact age of the lower tube. It is very likely that this lower tube was manufactured prior to 1994 and would need to have been replaced or modified to comply with the service bulletin.

The construction of the upper tube was consistent with SB-AG-31, which was issued 2 years before SB-AG-36.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors. 

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the ground strike involving Ayres Corporation S2R-T15, registration VH-IWI at Trangie, New South Wales on 31 August 2022.

Contributing factors
  • A fatigue crack initiated in the lower steel tube of the left shock assembly, located at the hole where the lower tube connected to the slider plate. The fatigue crack grew until there was a final overstress failure of the lower tube during the take-off roll.
  • For reasons not identified, it was highly likely that the lower tube of the left landing gear shock assembly was not replaced or modified to comply with SB-AG-36, which was issued to prevent similar failures.

Sources and submissions

Sources of information

The sources of information during the investigation included the:

  • pilot of the occurrence flight
  • Civil Aviation Safety Authority
  • Thrush Aircraft
  • maintenance organisation for VH-IWI

References

Main Landing Gear Shock Strut Inspection and Repair, Service Bulletin: SB-AG-31, Ayres Corporation, 3 November 1992. [Online]. Available: https://thrushaircraft.com/support/technical-publications/Service%20Bulletins/sb-ag-31%20MAIN%20LANDING%20GEAR%20SHOCK%20STRUT%20INSPECTION%20AND%20REPAIR.pdf [Accessed: 18 November 2022].

Main Landing Gear Shock Strut Modification, Service Bulletin: SB-AG-36, Ayres Corporation, 25 March 1994. [Online]. Available: https://thrushaircraft.com/support/technical-publications/Service%20Bulletins/sb-ag-36%20MAIN%20LANDING%20GEAR%20SHOCK%20STRUT%20MODIFICATION.pdf. [Accessed: 18 November 2022].

Maintenance Manual Model S2R-T15 Model S2R-T34, Serial Numbers T15-020 & Subsequent Numbers T34-091 & Subsequent Numbers, Thrush Aircraft Inc., 25 October 1990. Revised: 24 July 1991.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the following directly involved parties:

  • pilot of the occurrence flight
  • maintenance organisation for VH-IWI
  • Civil Aviation Safety Authority
  • Thrush Aircraft

No submissions were received.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2023

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     In 2003, Ayres Corporation’s assets were purchased by Thrush Aircraft, the current producer of the aircraft.

[2]     The main landing gear shock strut reduces the landing loads transmitted from the landing gear to the fuselage.

[3]     Main Landing Gear Shock Strut Inspection and Repair, Service Bulletin: SB-AG-31, Ayres Corporation, 3 November 1992. [Online]. Available: https://thrushaircraft.com/support/technical-publications/Service%20Bul…. [Accessed: 18 November 2022].

[4]     A rosette weld, also known as a plug weld, is a process that fuses two metals together by making a weld inside small circular holes.

[5]     Main Landing Gear Shock Strut Modification, Service Bulletin: SB-AG-36, Ayres Corporation, 25 March 1994. [Online]. Available: https://thrushaircraft.com/support/technical-publications/Service%20Bul…. [Accessed: 18 November 2022].

[6]     The drawing number together with the component identifier was considered the ‘part number’.

[7]     The reinforcing tube was around 3mm thick and 35 mm long, while the pre-1994 reinforming was described as 0.12” (3.0 mm) thick and 1 3/8” (34.9 mm) long.

Occurrence summary

Investigation number AO-2022-042
Occurrence date 31/08/2022
Location Trangie
State New South Wales
Report release date 06/04/2023
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Ground strike
Occurrence class Serious Incident
Highest injury level None

Aircraft details

Manufacturer Ayres Corporation
Model S2R-T15
Registration VH-IWI
Serial number T15-007
Aircraft operator ASHBY AVIATION PTY LTD
Sector Turboprop
Operation type Part 138 Aerial work operations
Departure point Trangie, Victoria
Destination Trangie, Victoria
Damage Minor

VFR into IMC and controlled flight into terrain involving Cessna R182, VH-EHM, 36 km north-west of Archerfield Airport, Queensland, on 29 August 2022

Final report

Report release date: 21/12/2023

Executive summary

What happened

At 0715 local time on 29 August 2022, a Cessna R182 Skylane RG (R182), registered VH-EHM, and operated by Executive Helicopters, departed a private property (Lighthouse) north-east of Roma, Queensland for an air transport flight under the visual flight rules (VFR) to Archerfield Airport. The aircraft departed with the pilot, 2 passengers, and a passenger’s pet dog on board.

As the aircraft attempted to cross a section of the Great Dividing Range, the pilot encountered forecast low cloud and reduced visibility, and was unable to find a way across. With limited fuel remaining, the pilot diverted to Dalby Airport and refuelled the aircraft before departing once again to find a different location to cross the elevated terrain.

After crossing a section of the Great Dividing Range at low level, the pilot tracked to the north of Amberley below low cloud towards an area adjacent to the D’Aguilar Range. While manoeuvring around the edge of this range, the aircraft collided with terrain during a turn, about 36 km north‑west of Archerfield. All occupants of the aircraft were fatally injured.

What the ATSB found

The ATSB found that the en route forecast available before departing Lighthouse predicted that the flight to Archerfield would be affected by low cloud, rain, fog and associated reduced visibility, particularly around the elevated terrain of the Great Dividing Range. After departing Lighthouse, the pilot encountered and manoeuvred at low level around forecast low cloud over elevated terrain of the range before diverting and landing at Dalby to refuel. An updated weather forecast available while at Dalby predicted similar conditions as previously forecast with additional periods of deteriorating weather around Amberley and Archerfield. However, the low cloud and deteriorating weather were expected to dissipate within the next 2-3 hours. The updated weather was not reviewed by the pilot while on the ground and, after refuelling, they subsequently departed once again toward forecast en route weather unsuitable for visual flight.

The pilot likely reviewed the updated weather forecast in-flight, shortly after take-off, but continued the flight at low level, and at normal cruise speed towards elevated terrain. After crossing a section of the Great Dividing Range below cloud and with minimal terrain separation, the pilot continued the flight in similar conditions toward the Lake Manchester VFR route adjacent to the D’Aguilar Range. While manoeuvring in this area, the aircraft very likely entered cloud resulting in the pilot losing visual reference with the ground and surrounding terrain, eventually leading to controlled flight into terrain.

There was no evidence of any conditions or circumstances likely to induce a medical problem or incapacitation for the pilot. There was also no evidence of any aircraft system or mechanical anomalies that would have influenced the accident. It was also considered unlikely that there was any direct or perceived organisational pressure on the pilot to continue the flight.

The pilot was probably influenced by plan continuation bias – an internal pressure or desire to get to the destination – to continue the flight, which probably became stronger as they got closer to Archerfield Airport. However, due to a lack of information, the ATSB was unable to determine the reasons why the pilot continued the flight at cruise speed and low level into unsuitable weather in the vicinity of known high terrain.

The investigation identified several other factors related to flight notification and fuel planning. Although these factors increased risk, they were not considered contributory to the accident.

Finally, the investigation found that the operator's hazard and risk register, which formed part of the organisation's safety management system, did not identify inadvertent entry into instrument meteorological conditions (IMC) as a hazard, which reduced the ability of the organisation to effectively manage the related risk.

What has been done as a result

The operator advised that they had removed aeroplane operations from their Air Operator's Certificate (AOC) and updated the hazard and risk register to include inadvertent entry into IMC. A risk assessment was conducted with the following risk controls planned to be implemented by February 2024 to minimise the risk of inadvertent entry into IMC for helicopter operations:

  • the operations manual is to be updated to include a formal organisational policy for supporting pilots to land or return to a safe landing site if they assess that they will be unable to maintain visual meteorological conditions.
  • annual operator proficiency checks will include inadvertent IMC avoidance and recovery techniques.

Safety message

The safety risks of visual pilots flying into non-visual conditions are well documented. This continues to be a recurring factor in aircraft accidents and has been the focus of numerous previous ATSB reports and publications.

A large amount of reference material is available to pilots for guidance on avoiding VFR flight into adverse weather as well as recovery should inadvertent IMC entry occur. The United States Aircraft Owners and Pilots Association Air Safety Institute website VFR into IMC provides an online course, videos and reference materials to assist pilots in avoiding and managing these scenarios. Additionally, the ATSB publication Avoidable Accidents No. 4, Accidents involving Visual Flight Rules Pilots in instrument Meteorological Conditions provides lessons learned from the analysis of various weather-related accidents and incidents.

Aviation safety risk management can be applied at all levels of aviation to enhance operational safety. For commercial operators, formalised risk management supports individual pilot decision making and provides a systemic approach to safety by introducing layers of controls to reduce single point of failure accidents.

As such, the ATSB strongly encourages operators to specifically assess the risk of inadvertent IMC and implement mitigation strategies commensurate to the level of risk it presents to their pilots and passengers.


The occurrence

On 28 August 2022 a Cessna R182 Skylane RG (R182), registered VH-EHM and operated by Executive Helicopters, flew from Archerfield Airport, Queensland to a private property (Lighthouse) north‑east of Roma, Queensland, with a pilot, 3 passengers, and a passenger’s pet dog on board.  

The following day, VH-EHM departed Lighthouse at 0715 local time with the pilot, 2 passengers, and pet dog, for an air transport[1] flight under the visual flight rules (VFR)[2] back to Archerfield (Figure 1). Recorded flight data showed the aircraft was initially established on a direct south‑easterly track towards Archerfield at cruise altitudes between 3,400 ft and 3,900 ft above mean sea level (AMSL).[3] The en route weather forecast valid at the time of departure indicated low cloud, rain, fog and associated reduced visibility (see the section titled Meteorological information).

At 0828, the pilot turned the aircraft left and descended to about 1,800 ft AMSL (about 600 ft above ground level (AGL))[4] before tracking north, then east towards the Biarra Range into a valley. The aircraft was then descended to about 1,200 ft (700 ft AGL), before the pilot completed a 180° turn at 300 ft AGL, climbed to 3,900 ft (2,000 ft AGL) and tracked towards Dalby Airport.

At about 0850, the pilot was contacted by a person via mobile phone. During the conversation, the pilot reported some weather on the range and their intention to refuel at Dalby before attempting to find another way to Archerfield. At 0901, the aircraft landed at Dalby and was refuelled with about 263 L of fuel.

Figure 1: Flight to Dalby Airport

Figure 1: Flight to Dalby Airport

Source: Google Earth and OzRunways, annotated by ATSB

Recorded data showed that VH-EHM departed Dalby at about 0912 and tracked southeast before climbing to a cruise altitude of about 2,500 ft (1,300 ft AGL). By 0927, the flight had progressed over rising terrain and, about 3 minutes later, was operating at about 2,300 ft (400 ft AGL) (Figure 2). At 0935, the pilot turned left towards Main Range, and about 8 km later, completed a 180° turn between 300–500 ft AGL before tracking south-east and climbing to about 2,500 ft (1,000 ft AGL).

At 0946, the aircraft passed over a mountain ridge at about 2,800 ft (200 ft AGL) before conducting a 90° left turn over another ridge at about 2,900 ft (270 ft AGL). VH-EHM then tracked to the north‑east and descended down the range to an altitude of about 1,200 ft (700 ft AGL).

Figure 2: Accident flight

Figure 2: Accident flight

Source: Google Earth and OzRunways, annotated by ATSB

At about 0955, the aircraft passed to the east of Gatton Airpark before tracking towards Lowood. After passing overhead Lowood, VH-EHM descended to about 700 ft (500 ft AGL) before turning east towards Fernvale and the D’Aguilar Range. The flight data showed that at 1005, the aircraft passed over a hill at a height of about 200 ft AGL, before climbing to 900 ft (700 ft AGL).

After passing Fernvale, the flight progressed down a valley before completing another 180° turn while climbing to 1,200 ft (1,000 ft AGL). After completing the turn, the aircraft was then descended to 800 ft (600 ft AGL) before turning right, back towards the D’Aguilar Range (Figure 3) and towards observed low cloud. During this turn, at 1007, the aircraft impacted terrain at an elevation of about 650 ft. The aircraft was destroyed, and the occupants were fatally injured.

Figure 3: Final flight track segment and accident site

Figure 3: Final flight track segment and accident site

Source: Google Earth and OzRunways, annotated by ATSB

Context

Pilot information

Qualifications and experience

The pilot held valid aeroplane and helicopter commercial pilot licences first issued in 1986 and 1990 respectively. The pilot’s last aeroplane flight review was conducted in March 2021 (valid until March 2023) and an annual operator proficiency check was last completed in March 2022 (also valid until March 2023). The pilot obtained a multi-engine command instrument rating in 1992, which was renewed 8 times,[5] with the last renewal completed in October 2002 (valid until October 2003). The pilot also held a helicopter night VFR rating that expired in May 2021, a helicopter low‑level rating,[6] and had completed a flight review for this rating in February 2022 (valid until February 2024).

The pilot first obtained their private pilot licences (aeroplane and helicopter) in 1976 and 1985 respectively and had accumulated experience in both fixed and rotary wing operations. At the time of the accident flight, the pilot had accumulated about 13,900 hours of aeronautical experience with over 12,000 hours in helicopters and over 1,000 hours in aeroplanes, of which about 470 hours were in command of the Cessna R182.

The pilot had about 96 hours of instrument flying experience and about 85 hours of night experience, with the last night flight conducted in April 2018.

The pilot had operated VH-EHM for 32.7 hours in the 30 days before the accident, which included several return flights from Archerfield to Lighthouse.

The pilot had also conducted aerial firefighting tasks throughout their aviation career and in June 2018 reported the following flight hours for different activities and environments:

  • air attack supervision, reconnaissance, and firebombing – about 200 hours
  • agricultural mustering[7] – 1,500 hours
  • low level flying – over 300 hours
  • mountainous terrain – 500 hours.
Recent history 

The pilot’s activities in the week before the accident, and on the day of the accident, were reported as being normal. The pilot’s next of kin stated that the pilot had been sleeping well with about 8‍–‍9 hours of sleep obtained each night. Other witnesses stated that the pilot was ‘very fit and healthy’ and not suffering any unusual personal or professional stress.

The day before the accident, the pilot woke at about 0530 and left for Archerfield Airport at about 0600. The pilot and passengers departed Archerfield in VH-EHM at 1055 and arrived at Lighthouse at about 1230. The pilot spoke to next of kin over the phone a few times during the day and had dinner at about 1800. The pilot sent a text message at 1945 indicating they were going to bed, however they also responded to an email at 2130. The next morning, a witness at Lighthouse did not notice anything abnormal during their interaction with the pilot before take-off at 0715. The pilot made and received some phone calls during the accident flight, including one after departing Dalby. The people who spoke to the pilot during the flight reported that they did not notice anything unusual or abnormal during these conversations.

The ATSB found no evidence to indicate that the pilot was experiencing a level of fatigue known to have an effect on performance.

Medical information

The pilot held a Class 1 aviation medical certificate, valid until October 2022. There were no indications of any significant medical problems in the pilot’s aviation medical records.

A post-mortem examination and toxicological analysis indicated no evidence of any pre-existing medical condition that could have contributed to the accident. The pilot’s toxicology report identified that carbon monoxide was present in the pilot’s system, but at a low level that was highly unlikely to cause impairment.

The pilot’s toxicology report also identified the presence of a medication in their system that was not documented on the medical examination questionnaires completed as part of their annual medical certificate renewals. This medication required approval for use by a designated aviation medical examiner (DAME) or by the Civil Aviation Safety Authority (CASA). The approval process required a 1-day ground trial of the medication, during which the pilot’s response to the medication would be assessed. The pilot was first prescribed this medication in 2019 by their DAME (who was also their general practitioner), who recalled that they likely advised the pilot to monitor for any symptoms or side effects. The DAME was unaware at that time that the medication required a ground trial and there was no evidence that this trial was conducted. The medication was not used on an on-going basis but was prescribed for a second time by the DAME in 2021.

The potential side effects of the medication were changes to colour vision, low blood pressure, dizziness, and blurred vision. The medication also had the potential to interact with another documented medication that the pilot had been taking regularly since 2010, although the potential interaction between them was classified as ‘minor’ with no significant interaction indicated by clinical studies. Nevertheless, patients had to be advised of the potential for interaction and were required to contact their doctor if they experienced symptoms such as dizziness, light‑headedness, or fainting.

The DAME reported that the pilot was health conscious and forthcoming in reporting any medical symptoms and that they had not reported any side effects from the use of the medication(s).

The ATSB considers it unlikely that the pilot was experiencing any side effects from the medication during the accident flight as they had probably used the medication previously (since 2019) and had not reported any adverse effects to their DAME. However, had the pilot been experiencing some of the medication’s known symptoms before the accident, it was probably insufficient to affect the ability of the pilot to fly the aircraft because:

  • the aircraft was under control during the entire flight and very likely so at the time of the accident.
  • radio calls made during the flight, and video footage of the pilot from Dalby Airport, did not indicate anything abnormal with the pilot.

Therefore, it was considered unlikely that the use of the medication adversely affected their performance during the accident flight. Additionally, while the medication was not documented on the pilot’s CASA medical records, its use was approved by the pilot’s DAME.

Relationship with passengers

There were 2 passengers on board VH-EHM on the day of the accident. The pilot’s next of kin and colleagues reported that the pilot and one of the passengers were close personal friends.

That passenger’s business had utilised the services of the operator (and accident pilot) for several years, and the pilot had flown the passenger to various private properties in Queensland numerous times. The passenger and their business were the operator’s most significant client at the time of the accident and had played a key role in the operator’s growth and success.

Passenger commitments

The passenger had a work-related meeting to attend at 0900 on the morning of the accident flight, however they notified a work colleague that they would not be able to attend the meeting due to the diversion to Dalby. The passenger’s next scheduled meeting was at 1530, which they communicated that they would likely be present for.

The work colleague reported that the passenger was generally not concerned about missing meetings if they could not get there in time. The passenger received business-related phone calls while on the ground at Dalby, and during the accident flight. People who spoke with the passenger during these calls reported that they did not notice anything unusual.

The other passenger on board had been communicating with friends during the flight using internet-based phone applications. Some messages sent by this passenger mentioned the poor weather encountered, the diversion to Dalby, and that they would be late for work. This passenger also contacted their employer at 0903 to advise that they would be late for work.

Aircraft information

The Cessna R182 Skylane RG is a 4-seat, high-wing, single-engine aircraft with retractable landing gear. The accident aircraft (Figure 4) was manufactured in the United States in 1978 and first registered in Australia in 1989. The aircraft was fitted with a Lycoming O‑540 piston engine driving a 3-blade Hartzell constant speed propeller and was equipped and approved for flight under both VFR and instrument flight rules (IFR).[8] The aircraft’s fuel tanks had a total maximum capacity of about 303 L, of which 284 L was useable.

Figure 4: VH-EHM

Figure 4: VH-EHM

Source: Robert Frola

The aircraft was equipped with an autopilot with lateral and vertical modes capable of maintaining altitude, airspeed, track, and wings level. The pilot’s next of kin reported that the pilot was familiar with using the autopilot, including the various modes. The aircraft’s original avionics had been upgraded to include 2 Garmin G5 electronic flight instruments, which provided redundant attitude, altitude, and airspeed information. The original mechanical altimeter and airspeed indicator had also been retained and the aircraft was also fitted with a JP Instruments FS-450, which provided fuel flow, fuel used, and fuel endurance information (Figure 5).

At the time of the accident, the aircraft had accrued about 5,858 hours of time in service. The most recent periodic maintenance inspection (100-hourly) was completed on 15 July 2022 and the aircraft had accrued about 30 hours of flight time since. There were no defects recorded on the aircraft’s current maintenance release,[9] and no scheduled maintenance was due.

The ATSB performed weight and balance calculations for the flight from Dalby based on the fuel quantity from the fuel upload, occupant and aircraft weights, and cargo weight. The calculations showed that the aircraft's take-off weight and centre of gravity were within limits.

Terrain awareness

The aircraft was fitted with a Garmin GTN 750Xi, which operated as both a radio communications unit and Global Navigation Satellite System[10] unit (Figure 5). The GTN 750Xi could operate in different modes and display a significant amount of information relating to management of the flight such as maps, airspace, and terrain.

Figure 5: VH-EHM instrument panel

Figure 5: VH-EHM instrument panel

Source: VH-EHM avionics maintainer, modified by ATSB

While not required to be fitted with a certified terrain awareness and warning system,[11] VH-EHM’s GTN 750Xi unit had a non-certified[12] terrain awareness function capable of predicting hazardous terrain conditions and issuing alerts. Terrain information was advisory only and could include:

  • display of altitudes of terrain and obstructions relative to the aircraft’s altitude
  • pop-up terrain alert messages (visual/auditory) issued when flight conditions met parameters set within the terrain system software algorithms. For example, an alert would be generated when the aircraft was above terrain during en route level flight but projected to come within 700 ft vertically of any obstacle, terrain, or powerline below or ahead of the aircraft.

The system also included a ‘terrain inhibit’ mode to deactivate the terrain alert message system.

Alerts from certified or non-certified terrain warning systems can be a nuisance or distraction to pilots when flying at altitudes below the alerting threshold of the system. In March 2023, the United States Federal Aviation Administration advised operators ‘…about the risks associated with distraction and complacency brought about by routine use of the…terrain inhibit feature…[and to] ensure operators understand the importance of having procedures and training for the use of the terrain inhibit aural warning switches associated with nuisance alerts’.[13]

The operator did not have any procedures or training on the use of the terrain awareness and warning system for the Garmin GTN 750Xi. The pilot was reported to usually have the terrain awareness system enabled unless conducting low level visual aerial firefighting operations where the terrain alerts could be a nuisance.

The ATSB was unable to establish whether the terrain awareness function was enabled or inhibited at the time of the accident. Had the terrain awareness system been enabled during the accident flight, the system’s alerting thresholds, coupled with the low-level flying, would likely have produced multiple alerts, potentially distracting the pilot. These factors would have limited the effectiveness of the terrain awareness system in preventing this accident.

Flight following system

All the operator’s aircraft, including VH-EHM, were equipped with a Spidertracks[14] unit with a dash mounted device (Figure 5). The units were fitted primarily to support contracted aerial work and the system was not normally activated for other flights. When powered on, the system entered ‘normal mode’, which would automatically record and transmit the aircraft’s position at regular intervals. A ‘Watch’ function could be manually activated by the pilot so that an alert would be sent out if communication with the aircraft was lost after 10 minutes. The pilot could also manually enable the ‘SOS’ function to signal an emergency or to alert pre‑determined personnel. When the emergency ‘SOS’ function was activated, the system was programmed to send out text messages and emails to operator personnel.

The operator did not receive any Spidertracks alerts from VH-EHM during the accident flight.

Certificate of airworthiness

The aircraft’s certificate of airworthiness (CoA) was issued in 1989 when it was registered VH‑HZU. After purchasing the aircraft in late 2019, the operator requested a change of registration to VH‑EHM, which was approved by CASA in January 2020, effective from 7 February 2020. The CASA approval noted that the aircraft could not be operated beyond 7 February 2020, unless a new CoA bearing the new registration mark was issued.

An application and relevant aircraft documentation was required to be submitted by the operator to CASA for the issue of the new CoA. However, neither the operator, nor CASA possessed any records to indicate that the application for the new CoA had been submitted or that the new CoA was issued. The original CoA was found in the on-site wreckage and showed the old registration mark (VH‑HZU) amended by pen to reflect the new registration mark (VH-EHM).

Terrain

The flight’s planned track toward Archerfield Airport took the aircraft from the low-lying plains of inland Queensland across an area of the Great Dividing Range to the west of Brisbane. Elevations within the range were generally between 1,500–2,000 ft AMSL, with numerous peaks between 2,000–2,700 ft (Figure 6).

Figure 6: Visual navigation chart extract showing terrain along the flight path

Figure 6: Visual navigation chart extract showing terrain along the flight path

Source: Airservices Australia and OzRunways, modified and annotated by ATSB

Meteorological information

Pilot weather requests

CASA regulations[15] required the pilot to review weather forecasts and reports, within 1 hour of commencing a flight, covering the route to be flown, the departure aerodrome, and the planned destination aerodrome. If an authorised weather forecast/report was not available, and the weather conditions at the departure aerodrome would permit the aircraft to return and land safely within 1 hour of take-off, the pilot could take-off without reviewing the weather. However, they were required to obtain the relevant weather information within 30 minutes of take-off or return to the departure aerodrome. The available evidence indicated that the relevant weather forecast information would have been available to the pilot while at Dalby via the internet, or by radio from Brisbane air traffic control.

Data from Airservices Australia indicated that the pilot logged in to the National Aeronautical Information Processing System (NAIPS)[16] 3 times in the 24-hour period before the accident. These were recorded on 29 August 2022 at 0708 and 0709 (shortly before departing Lighthouse), and 0925 (about 13 minutes after departing Dalby).

The data accessed by the pilot in NAIPS included Terminal Area Forecast (TAF)[17] and METAR[18] for aerodromes relevant to the flight (Archerfield, Amberley and Toowoomba). Weather products, such as the graphical area forecast (GAF), and grid point wind and temperature, could also be viewed by the pilot, but access to these were not logged by NAIPS. Therefore, the investigation could not determine whether the pilot reviewed that information.

Forecast

Departure from Lighthouse

Two GAFs[19] issued by the Bureau of Meteorology (BoM) at 0225 on 29 August covered the planned direct route from Lighthouse to Archerfield and were valid from 0300–1500.

The weather forecast from Lighthouse towards the Great Dividing Range was generally suitable for VFR flight. However, from the Great Dividing Range to Archerfield, the forecast included broken[20] stratus cloud from 1,500 ft to 2,500 ft (becoming scattered from 1200), scattered cumulus cloud between 2,500 ft and 6,000 ft, and broken stratocumulus cloud from 5,000 ft to 7,000 ft. Visibility below the cloud layer was greater than 10 km.

Moderate isolated showers of rain were expected to reduce visibility to less than 3,000 m in broken stratus cloud between 1,000 ft and 2,500 ft, and in broken cumulus from 2,500 ft to 8,000 ft. The forecast predicted isolated fog over land areas which would reduce visibility to less than 300 m and was expected to dissipate after 0900. Isolated smoke below 3,000 ft was also forecast with associated reduced visibility of 4,000 m and extending up to 4,000 ft after 0900.

TAFs were also issued for relevant aerodromes along the planned route. Toowoomba had forecast broken cloud at 200 ft AGL (2,303 ft AMSL), mist with 2,000 m visibility, and a 40% probability of fog with 400 m visibility. Amberley had forecast light showers of rain, scattered cloud at 2,000 ft AGL (2,091 ft AMSL), broken at 4,000 ft AGL (4,091 ft AMSL), and greater than 10 km visibility below the cloud layer. Archerfield had forecast light showers of rain, few cloud at 2,000 ft AGL (2,065 ft AMSL), broken at 3,500 ft AGL (3,565 ft AMSL), and greater than 10 km visibility below the cloud layer.

The grid point wind and temperature chart for the region issued at 0359 and valid from 0700–1000 forecast:

  • easterly winds between 9–13 kt at 1,000 ft, with temperatures of 12–14 °C
  • easterly winds between 13–21 kt at 2,000 ft, with temperatures of 11–13 °C
  • north-easterly winds between 8–20 kt at 5,000 ft, with temperatures of 7–10 °C.

Departure from Dalby

An updated GAF was issued at 0819 valid for the period from 0900–1500 with some differences to the previous forecast.  

The updated forecast predicted that the previously forecast broken stratus cloud from 1,500 ft to 2,500 ft would reduce to scattered at 1100 and then dissipate by 1200, with broken cumulus and stratocumulus cloud between 3,000 ft and 7,000 ft. Visibility remained greater than 10 km below the cloud layer. The previously forecast moderate isolated showers of rain continued, as did the isolated smoke which extended up to 6,000 ft with an increased visibility of 6,000 m.

An amended TAF was also issued for Amberley at 0851, which included the same rain, cloud, and visibility forecast as the previous TAF but with an INTER[21] period between 0900 and 1100 where visibility reduced to 6,000 m in light showers of rain, with cloud broken at 1,500 ft AGL (1,591 ft AMSL). The Archerfield TAF was also amended at 0831 to include scattered cloud now forecast at 1,500 ft AGL (1,565 ft AMSL), broken at 3,000 ft AGL (3,065 ft AMSL), and an INTER period between 0900 and 1000 where visibility reduced to 4,000 m in moderate showers of rain.

The above forecasts were available when the aircraft was on the ground at Dalby and also when the pilot requested the weather at 0925 – 13 minutes after take-off. At this time, an amended TAF issued at 0914 (after departure from Dalby) was also available for Toowoomba which forecast broken cloud at 100 ft AGL (2,303 ft AMSL), and fog with 300 m visibility.

Observations

The following cloud and visibility observations were recorded or derived at weather stations along the aircraft’s flight path (Figure 7).

Table 1: Cloud and visibility observations

TimeLocationCloud baseVisibility (m)
0900Dalby2,500 ft AMSL (2,500 ft AGL) [1]- [2]
0930Oakey2,531 ft AMSL (1,200 ft AGL)>10 km
0930Toowoomba2,203 ft AMSL (100 ft AGL)150 m
1000Gatton1,542 ft AMSL (1,250 ft AGL)-
1000Amberley1,491 ft AMSL (1,400 ft AGL)>10 km
1000Beaudesert1,657 ft AMSL (1,500 ft AGL)-
1000Greenbank636 ft AMSL (500 ft AGL)-
1000Archerfield1,965 ft AMSL (1,900 ft AGL)>10 km
1022Amberley791 ft AMSL (700 ft AGL)4,000

[1] The automatic weather stations at Dalby, Gatton, Beaudesert and Greenbank did not have a ceilometer to record cloud base. The cloud base was estimated from the temperature‑dewpoint spread. Dewpoint is the temperature at which water vapour in the air starts to condense as the air cools. It is used, among other things, to monitor the risk of aircraft carburettor icing or the likelihood of fog.

[2] The automatic weather stations at Dalby, Gatton, Beaudesert and Greenbank did not have a visibility meter.

Figure 7: Weather station locations and flight track

Figure 7: Weather station locations and flight track

Source: Google Earth and Bureau of Meteorology, annotated by ATSB

Video camera footage

Surveillance video cameras from Lowood and Fernvale provided information on the weather around the time of the accident. The field of view of each camera was determined (Figure 8), alongside identifiable mountain peaks (labels A to E).

Figure 8: Map showing camera field of views, identifiable points (A to E), and flight track

Figure 8: Map showing camera field of views, identifiable points (A to E), and flight track

Source: Google Earth and Geoscience Australia, modified and annotated by ATSB

The surveillance video camera from Lowood, located about 10.5 km west-south-west of the accident site, captured the aircraft flying overhead below a low-level cloud layer about 4 minutes before the accident. No abnormal engine or propeller sounds were noted. A mountain peak (A) about 7.8 km from the camera location was just visible (Figure 9).

Figure 9: Image from Lowood towards D’Aguilar Range at the time of flyover

Figure 9: Image from Lowood towards D’Aguilar Range at the time of flyover

Source: Lowood Golf Course, modified and annotated by ATSB

Another surveillance video camera from Fernvale, located about 4.2 km south-west of the accident site, provided video observations of the weather conditions surrounding the accident site. An exemplar image from the video is provided to show identifiable peaks of the D’Aguilar Range and their elevations in clear conditions (Figure 10).

Figure 10: Image from Fernvale showing the D’Aguilar Range in clear conditions

Figure 10: Image from Fernvale showing the D’Aguilar Range in clear conditions

All heights AMSL.

Source: Fernvale Rural Fire Brigade, modified and annotated by ATSB

Video footage of the conditions around the time of the accident[22] (Figure 11) showed low level cloud over the area of the D’Aguilar Range, with mountain peaks B and C, and the accident site, obscured by cloud. The aircraft could not be seen in the footage.

Figure 11: Image from Fernvale around the time of the accident

Figure 11: Image from Fernvale around the time of the accident

All heights AMSL.

Source: Fernvale Rural Fire Brigade, modified and annotated by ATSB

Witness observations

Several witnesses along the aircraft’s route from Dalby to Fernvale recalled seeing the aircraft flying at low altitude below cloud. The witness closest to the accident site in Fernvale reported a low flying Cessna heading east towards the D’Aguilar Range with the wings level and undercarriage retracted. They recalled the aircraft banking left and disappearing from view due to cloud. The witness also reported heavy low cloud, light rain, and fog in the Fernvale area at the time.

Visual flight rules

CASA regulations[23] outlined that flight under the VFR could only be conducted in VMC with the criteria provided in the CASR manual of standards and the CASA Visual Flight Rules Guide.

The flight from Dalby, and the location of the accident, were in Class G (non-controlled) airspace. The following VMC were stipulated for flight under the VFR in Class G airspace at or below 3,000 ft or 1,000 ft above ground level (whichever was higher):

  • clear of cloud and in sight of the ground or water
  • a flight visibility of 5,000 m.

Amberley was in Class C (controlled) airspace. The following VMC were stipulated for flight under the VFR in Class C below 10,000 ft above ground level:

  • 1,500 m horizontally from cloud
  • 1,000 ft vertically from cloud
  • a flight visibility of 5,000 m.

Archerfield was in Class D (controlled) airspace. The following VMC were stipulated for flight under the VFR in Class D (all heights):

  • 600 m horizontally from cloud
  • 1,000 ft vertically above cloud, 500 ft vertically below cloud
  • flight visibility of 5,000 m.

Special VFR

By day, when VMC did not exist, pilots could request, and be issued, a ‘special VFR clearance’ from air traffic control responsible for a control zone (CTR) or control area (CTA). The clearance allowed for flight in a CTR, or in a CTA next to a CTR, for the purpose of entering or leaving a CTR, providing an IFR flight would not be unduly delayed. When operating under a special VFR clearance the pilot was responsible for ensuring that the:

  • flight could be conducted clear of cloud
  • visibility was not less than 1,600 m (for aeroplanes).

Requirements for maintaining visual conditions

VH-EHM was an IFR‑equipped aircraft and the pilot had previous instrument flying experience, although not current at the time of the accident. Additionally, passenger air transport flights conducted under CASR Part 135 in single-engine piston-powered aircraft were prohibited from operating under the IFR.[24] Despite that restriction, the aircraft was also in a radar coverage area with air traffic control support available to the pilot from either Amberley or Brisbane in the event emergency assistance due to flight in instrument meteorological conditions (IMC)[25] became necessary. The ATSB was unable to determine the extent to which compliance with the requirement to remain in VMC influenced the pilot’s decision to remain at low level, near terrain, in reduced visibility rather than climbing into cloud at higher altitudes above terrain.

The flight conduct section of the operator’s operations manual stated:

Company aircraft shall not commence a VFR flight unless current meteorological reports and forecasts show that the weather conditions en-route and at the destination are such that the flight can be conducted under the visual flight rules.
If weather conditions begin to deteriorate, the pilot in command must carefully monitor the changes and plan possible alternative action.

Similarly, the emergency procedures section of the operations manual stated:

Company pilots shall divert and land at the nearest suitable aerodrome or return to the departure point if meteorological conditions are encountered which are not suitable for continued flight.
Minimum height

In addition to minimum visibility and distance from cloud requirements, a pilot was also required to maintain a minimum height above the ground. Unless during take-off, landing or other approved low-flying operation, the CASR[26] detailed that a pilot in command must not fly an aeroplane over:

  • a populous area or public gathering below 1,000 ft above the highest feature or obstacle within a horizontal radius of 600 m of the point on the ground or water immediately below the aeroplane 
  • any other area at a height lower than 500 ft above the highest feature or obstacle within a horizontal radius of 300 m of the point on the ground or water immediately below the aeroplane.

These minimum heights did not apply if it was essential, through stress of weather or any other unavoidable cause, that a lower height be maintained.

Recorded Data

Recorded data was obtained from various sources during the investigation, as follows:

  • OzRunways[27] flight track data (altitude, ground speed, heading) was available for the entire flight up until about 8 seconds before the accident.
  • The pilot made 3 radio broadcasts on the Dalby common traffic advisory frequency[28] during the flight — an inbound call at 0855, left base call at 0859, and a taxi/departure call at 0911. Review of this audio did not indicate anything abnormal with the flight or the pilot.
  • While at Dalby, airport video footage captured the aircraft’s taxi to the refuel location, refuel, and taxi out to the runway. Once the aircraft had taxied and was stationary near the fuelling location, the pilot remained inside the cockpit for about 20 seconds before disembarking. The pilot spent the next 9 minutes refuelling the aircraft before re‑entering the cockpit, and 30 seconds later, the aircraft taxied back out to the runway.
  • The aircraft made 4 significant turns during the accident flight including 2 course reversals. Based on flight data, the 2 turns around the Main Range (including a 180° course reversal) had estimated average bank angles of 35° and 39°. The 2 turns near the D’Aguilar Range (including the turn leading up to the accident) averaged 38° and 36° indicating they were made in the course of controlled flight similar to the previous turns (Figure 12).
  • The aircraft was flown below 500 ft AGL[29] on several occasions during the accident flight, with the lowest being about 200 ft AGL (Figure 13). Since the terrain elevation data did not account for vegetation or structures, it was likely that there were lower vertical clearances during the flight.
  • The flight track data indicated that the aircraft’s ground speed after departing Dalby was generally between 120–140 kt, about the normal cruise speed for the R182.
  • Surveillance video footage from a private property in Fernvale, located about 2.3 km south‑west of the accident site, captured the sound of the aircraft as it flew over Fernvale, up to the time of impact with terrain. The sound of the engine and propeller could be heard up to the time of impact with no abnormal engine or propeller sounds noted.

Figure 12: Significant turns during flight

Figure 12: Significant turns during flight

Source: Google Earth and OzRunways, annotated by ATSB

Figure 13: Low-level flight over Main Range

Figure 13: Low-level flight over Main Range

Source: Google Earth and OzRunways, annotated by ATSB

On-board recording devices

The aircraft was not fitted with a flight data recorder or cockpit voice recorder, nor was it required to be. There have been numerous investigations undertaken by the ATSB that would have been significantly assisted by the availability of recorded data. Such information would likely have provided additional detail about the events that led to the development of these accidents, and possibly allowed for timely identification and resolution of safety issues.

The ATSB investigation report AO-2017-118 into the collision with water involving de Havilland Canada DHC-2, in Jerusalem Bay, New South Wales in 2017 identified and directed the following safety issue to CASA:

Australian civil aviation regulations did not mandate the fitment of flight recorders for passenger‑carrying aircraft under 5,700 kg. Consequently, the determination of factors that influenced this accident, and other accidents have been hampered by a lack of recorded data pertaining to the flight. This has likely resulted in the non‑identification of safety issues, which continue to present a hazard to current and future passenger-carrying operations.

In October 2021, the ATSB received advice from the International Civil Aviation Organization (ICAO) that the recommendation for fitment of lightweight and airborne image recorders in aircraft less than 5,700 kg used in passenger carrying operations will be referred to an ICAO Working Group for further study and consideration. In May 2023, the coronial inquest relating to the Jerusalem Bay accident recommended that CASA engage with the ATSB on the subject of mandatory fitment of on-board recording devices.

There have been several recent examples of investigations where the use of recording devices, although not required by regulations, has assisted in determining important safety factors related to the incident under investigation. A recent example was the VFR-into-IMC, loss of control, and collision with terrain involving Airbus Helicopters EC130 T2 near Mount Disappointment, Victoria in 2022 which resulted in 5 fatalities, including 4 fare-paying passengers.

The aircraft was fitted with a device that recorded video imagery and audio data from inside the aircraft cabin, as well as GPS inertial and positioning data, which assisted the investigation. Fitment of a similar device to VH-EHM may have been of value to this accident investigation to understand the specific environmental conditions faced by the pilot, insights into the pilot’s weather-related decision making, and any pilot-passenger interactions during the flight.

Site and wreckage information

The accident site was located within the D’Aguilar Range on a steep section of mountainous terrain covered with trees (Figure 14).

Figure 14: Accident site

Figure 14: Accident site

Source: ATSB

There were several initial impact points with numerous trees before the aircraft impacted the ground. These indicated a final flight path descent angle of about 2°, in about a 47° right bank (Figure 15).

Figure 15: Representation of the aircraft’s attitude at time of impact with trees

Figure 15: Representation of the aircraft’s attitude at time of impact with trees

Source: ATSB

The aircraft impacted terrain at 650 ft AMSL, about 28 ft vertically below the top of the ridge. The wreckage trail extended about 40 m from the initial impact point to the top of the ridge where most of the wreckage, including the engine, was located. The propeller was located about 10 m forward of the main impact point.

On-site examination of the engine did not reveal any pre-impact mechanical damage, while damage to the propeller indicated that the engine was providing high power at impact. The landing gear and flaps were retracted and there was no evidence of an in-flight break-up or a pre‑existing defect with the aircraft. Due to extensive damage, the serviceability of the flight instruments, auto‑pilot, and associated systems could not be determined. The pressure altimeter subscale QNH[30] setting was appropriately set. The fuel tanks ruptured on impact, and an odour of fuel was present at the site. No fuel samples were available for recovery.

A tablet and 3 mobile phones were retrieved from the accident site, however the ATSB was unable to recover any data from these devices due to substantial damage to their internal components.

Survivability aspects

Examination of the aircraft wreckage indicated that the impact was at high speed into steep rising terrain and was not survivable.

Emergency locator transmitters

Emergency locator transmitters (ELT) and/or portable beacons are carried on aircraft so that in the event of an accident in a remote location, the aircraft wreckage and its occupants can be located quickly and efficiently by search and rescue (SAR) operations.

Under CASA regulations,[31] at the time of the accident, the aircraft was required to carry either:

  • a portable ELT – an emergency position indicating radio beacon (EPIRB), or a personal locator beacon (PLB). These are handheld and usually require manual activation.
  • an automatic ELT – usually mounted to the airframe and activated automatically during a crash, typically by a g-force[32] activated switch.

A review of the available maintenance documentation identified some inconsistencies regarding the aircraft’s ELT carriage requirements. As part of the aircraft’s maintenance schedule, the automatic ELT’s battery was periodically inspected by the avionics provider and was last replaced in 2019, with replacement due in 2024. The battery condition was last inspected by the avionics provider in July 2022 and was found to be serviceable. However, the aircraft’s maintenance organisation had annotated the aircraft’s current maintenance release to require the carriage of a portable ELT for flight.

The annotation for carriage of a portable ELT first appeared in a maintenance release in March 2020. Of the following 9 maintenance releases, the portable ELT annotation only appeared on 4, with one of those entries crossed out and signed by the maintainer indicating that it was likely annotated in error. The operator similarly understood the annotations on the maintenance releases requiring carriage of a portable ELT to be incorrect as the aircraft was fitted with an automatic ELT and that the pilot had previously spoken to the maintenance organisation to correct this.

During the on-site investigation, an automatic ELT and its antenna were observed to be physically fitted to the aircraft, but its serviceability and whether it was in the armed position was not determined. There were no signals received from the automatic ELT at the time of the accident and no portable ELT (PLB or EPIRB) was able to be located at the accident site.

Data from a 2013 ATSB research report indicated that ELTs function as intended in about 40% to 60% of accidents in which their activation was expected. Various factors can affect activation such as flat batteries, incorrect installation, not arming the ELT, lack of fire protection, and impact damage. The ATSB could not determine why the ELT did not function in this accident.

Flight notification

Requirements

Regulations[33] required pilots conducting VFR air transport flights to follow one of the following flight notification processes:

  • submit a flight plan to Airservices Australia
  • nominate a SARTIME[34] for arrival to Airservices Australia
  • leave a flight note[35] with a ‘responsible person’.

A ‘responsible person’ was required to meet the following requirements:

  • be over the age of 18 years
  • have access to at least 2 operative and appropriate means of communicating with SAR (for example, 2 telephones)
  • satisfy the pilot in command that the person:
    • knows how to contact the Joint Rescue Coordination Centre (JRCC)
    • will immediately do so if the pilot in command’s flight is overdue.

The operator’s procedures required that a flight notification be submitted via electronic, verbal or written means for all air transport flights. If the notification was not submitted to Airservices Australia, then a SAR form was to be completed and provided to the operator or a client (passenger) representative who was to be briefed on the SAR procedure.

The SAR form included information such as the route, SARTIME, and a ‘Next Call’ time. Pilots were required to contact the person holding the SAR form by the ‘Next Call’ time or by the SARTIME. If no contact was made within 15 minutes of these times, the person holding the SAR form would contact the operator’s head of flying operations (or their delegate) and the relevant procedures from the operator’s emergency response plan would be initiated, which included contacting JRCC after 30 minutes.

VH-EHM’s operator advised that the pilot would usually either leave the flight notification with the operator’s line pilot if they were on duty, or with a family member who was not associated with the operator. The line pilot was not on duty on the day of the accident.

Accident flight

The aircraft departed Lighthouse at 0715 on 29 August 2022. About 30 minutes after departing, the pilot contacted a family member and advised them to expect their arrival ‘late morning’. The family member was expecting the pilot to arrive at Archerfield between 1030 and 1100, and to receive a call from the pilot upon landing. They stated that they were not provided with any information about what actions to take if the aircraft became overdue.

The family member attempted to contact the pilot on several occasions between 1120 (one hour and 13 minutes after the accident) and 1240 but was unsuccessful. They subsequently raised concern about the flight by notifying the operator via email at 1309 that they were unable to contact the pilot. The operator then attempted unsuccessfully to contact the pilot, and subsequently checked publicly available ADS-B[36] data to check the aircraft’s last recorded position, which was over the Lowood Golf Club. The operator then made several calls to individuals at various nearby locations to see whether the aircraft had landed somewhere other than Archerfield.

At 1331, the operator notified Lowood police and at 1342, arranged for a helicopter from another Archerfield based operator to search for the missing aircraft near the last recorded location. At 1344, the operator notified Airservices Australia who coordinated a SAR effort with the JRCC.

At about 1427 (4 hours and 20 minutes after the accident), the helicopter arranged by the operator departed Archerfield and located the wreckage shortly after. The helicopter was landed near the wreckage and its pilot proceeded to the site on foot, reporting back to the operator that none of the occupants had survived. Shortly after, a SAR helicopter arrived at the site with paramedics confirming the previous report.

Operational information

Fuel planning

The CASR[37] prescribed the fuel requirements for air transport flights conducted under CASR Part 135 which were also reflected in the operator’s operations manual. At a minimum, the aircraft had to carry the following amounts of usable fuel before a flight commenced:

  • taxi fuel – fuel used before take-off
  • trip fuel – fuel for take-off, climb, cruise, descent, and landing
  • contingency fuel – 10% of trip fuel for a piston engine aeroplane
  • final reserve fuel – 45 minutes flight time for a piston engine aeroplane (between 24–30 L for VH‑EHM)[38]
  • if required – destination alternate fuel, holding fuel, and additional fuel.

Also, the effect of operational conditions such as the aircraft’s weight, and relevant meteorological reports and forecasts had to be considered during fuel planning.

To determine the required quantity of usable fuel for a flight, fuel consumption data from either the operator’s fuel consumption monitoring system or aircraft manufacturer data could be used. Operators conducting air transport flights under CASR Part 135 were required to complete a ‘journey log’ before and after each flight and include information such as fuel on-board before the flight and after landing. The operator required the quantity of fuel on-board before each flight be determined using 2 independent means.

Fuel records were available for the operator’s helicopters, but no fuel records could be found for VH-EHM. Fuel was available at Lighthouse and was primarily used for filling up helicopters involved in cattle mustering. VH-EHM could be re-fuelled at the property but required some additional effort to set up the fuel drum and pump for fuel delivery. Prior to departure on the morning of the accident flight, VH-EHM was not refuelled at Lighthouse. No information was available about the pilot’s fuel planning for the flight from Lighthouse to Archerfield.

Fuel calculations

After departing Lighthouse and encountering weather on the range, the pilot diverted to Dalby to refuel. An assessment was undertaken to estimate the quantity of fuel on-board the aircraft when it departed Lighthouse, and if that quantity was sufficient for the intended flight to Archerfield (see Appendix – Fuel calculations).

Depending on the fuel flow data used for the calculations, the aircraft was estimated to have had between 100–125 L of useable fuel on‑board (of a total useable capacity of 284 L) before departing Lighthouse. Calculations showed that the aircraft had sufficient fuel on-board to complete the flight to Archerfield (taxi fuel and trip fuel) in ideal weather conditions but was required to land with between 31–39 L of useable fuel (contingency fuel and final reserve fuel). As a result, it was estimated that the aircraft would have landed at Archerfield with between 4–13 L below the minimum required useable fuel in ideal weather conditions.

In addition, even had this minimum required fuel been on-board, it would have been insufficient fuel to account for a weather-related diversion. Weight and balance calculations showed that the aircraft fuel tanks could have been filled completely with the available fuel at Lighthouse while remaining below the allowable maximum take-off weight.

Airspace

The Amberley military control zone extended from ground level up to an altitude of 8,500 ft surrounding Royal Australian Air Force Base Amberley (Figure 16). NOTAMs[39] applicable on the day of the accident established that the Amberley controlled airspace was active from 0800 to 2300 and required an airways clearance to transit. Transit through the Amberley control zone provided the lowest terrain elevations for flights between Archerfield and areas west of the controlled airspace.

In March 2021, Amberley air traffic control notified Archerfield operators that pilots needed to plan flights around the Amberley control zone and should not plan for, or expect to receive, a clearance when departing from or arriving into Archerfield. This was due to an increase in the volume and complexity of traffic in the area, in combination with Brisbane airspace changes.

Figure 16: Amberley control area

Figure 16: Amberley control area

Source: Airservices Australia, annotated by ATSB

Flights bound for Archerfield from the west of the Amberley CTR generally tracked around Amberley controlled airspace, either from the north using the Lake Manchester VFR route or from the south using the points of Mount Walker, Flinders Peak, and Spring Mountain (Figure 16). These routes enabled pilots to fly visually under or around restricted airspace without requiring an airways clearance from Amberley air traffic control.

Lake Manchester VFR route

The Lake Manchester VFR route was a corridor under the restricted airspace from ground level to 1,500 ft AMSL (less than 1,000 ft AGL in some sections). The lateral separation from Amberley controlled airspace and elevated terrain reduced to about 1 km at some points, and there was a powerline that passed under a section of the route. Flying south via the mountain peaks required maintaining the aircraft below the 2,500 ft AMSL restriction (associated with the R612B restricted airspace), and above elevated terrain exceeding 600 ft AMSL.

The pilot’s next of kin and a former colleague reported that the pilot had flown the Lake Manchester VFR route, and the route south of Amberley airspace, numerous times in helicopters and aeroplanes and was very familiar with the terrain. The former colleague also reported that the pilot did not recommend using the Lake Manchester VFR route if the weather was poor around the D’Aguilar Range, due to the rising terrain and limited separation from controlled airspace. Transit through the low-lying terrain of the Amberley control zone was preferred in those circumstances.

The operator reported similar concerns associated with the use of the Class G airspace (uncontrolled) surrounding Amberley and the Lake Manchester VFR route, particularly in marginal weather conditions due to the:

  • rising terrain to the north and east of the Lake Manchester VFR route
  • limited lateral separation between controlled airspace and rising terrain in some areas of the route
  • need for aircraft to remain below 1,500 ft while also remaining above the terrain and power lines, with potential for east and west bound traffic
  • potential for the range to the north of the route to create problematic weather
  • occurrence of regular airspace infringements in the area.

CASA Office of Airspace Regulation

The CASA Office of Airspace Regulation (OAR) advised that VFR routes, which were usually established following feedback from local airspace users, were only to be used in VMC and generally followed identifiable ground features to ease visual navigation. The OAR further stated that in non‑controlled airspace, pilots were responsible for aircraft separation, terrain clearance, and being appropriately briefed for the flight.

Aeronautical studies and airspace reviews undertaken by the OAR generally involved consultation with the aviation community as well as review of ATSB and Airservices Australia incident data. While there were several reported airspace infringements into the Amberley controlled airspace, in the period from January 2020 to May 2023 there were no CASA aviation safety incident reports recorded relating to the Lake Manchester VFR route, except for the accident involving VH-EHM.

A review of data by the Royal Australian Air Force concluded that infringements of the Amberley controlled airspace were primarily due to pilots not reviewing NOTAMs and an over reliance on electronic flight bags, which in some instances did not accurately display the activity status of military restricted areas.

The OAR considered that the risk associated with defence-related aircraft movements within the Amberley airspace and the segregation of these activities with civil aviation activities was appropriate. The OAR also noted that there was ongoing work by CASA, the Australian Defence Force, and Airservices Australia to reduce airspace infringements by educating pilots on the use of military airspace, including via the publication of guidance material. For example, an infringement from 2017 involved a VFR flight where the pilot was tracking along the Lake Manchester VFR route and requested clearance to transit the Amberley control zone. The clearance was denied by Amberley air traffic control due to other traffic in the area. Unknown to Amberley ATC, the pilot was deviating around weather and subsequently inadvertently entered the Amberley control zone. The Royal Australian Air Force advised pilots facing similar circumstances:

If you are experiencing difficulties (such as bad weather or aircraft issues), advise ATC as early as possible as they may be able to provide you with priority.

Conclusion

The ATSB concluded that there was insufficient evidence to indicate that the structure of the Amberley controlled airspace in relation to the Lake Manchester VFR route contributed to this accident. While acknowledging the narrow lateral and vertical separation between terrain and controlled airspace on the route, it was a published area of airspace intended for use only in VMC.

Furthermore, the route was known to the pilot as being an area to avoid in adverse weather, which existed at the time of the accident, when safety margins would be greatly reduced. In the event of encountering adverse weather along the route making it unsuitable, there remained an alternative in‑flight option of requesting an airways clearance to enter Amberley airspace to either land or transit.

The NAIPS login records indicated that the pilot requested NOTAM information during each NAIPS request and was tracking around Amberley controlled airspace towards the end of the flight. Therefore, the pilot was likely aware it was active at the time, and that it required an airways clearance to transit. However, a review of air traffic control recordings did not identify any radio communications or requests for an airways clearance between VH-EHM’s pilot and Amberley air traffic control.  

A pilot previously employed by the operator between January 2021 and June 2022, reported that in their experience, requests to transit Amberley were usually denied. However, there was no information available on the accident pilot's past experience with requesting and being granted/denied Amberley transit clearance, or of their views on the 2021 Amberley notification to Archerfield operators regarding flight planning around the Amberley CTR. Therefore, the investigation was unable to determine whether these considerations influenced their decision not to request a transit clearance.

Organisational information

Executive Helicopters was an Archerfield based operator established in 2008. The pilot joined the operator as chief pilot in 2009 – later retitled head of flying operations (HOFO) – after which commercial helicopter operations commenced. Single-engine piston-powered aeroplane VFR charter[40] (air transport) operations were added to the AOC in 2020 after VH-EHM was purchased.

The operator held an Air Operator’s Certificate (AOC) issued by CASA which was valid at the time of the accident. The AOC authorised the certificate holder to operate various single-engine helicopters, as well as single-engine piston‑powered aeroplane types with a maximum take-off weight not exceeding 5,700 kg, on VFR air transport and aerial work operations.

From 2009 to 2021, the accident pilot was the only full-time pilot conducting operations under the AOC. Over this time, casual pilots were also contracted to undertake flying as required. A second full‑time pilot was employed from January 2021 to June 2022 and a third joined shortly before the accident.

At the time of the accident, the operator’s staff consisted of the HOFO (the accident pilot), one line pilot, an administrative compliance assistant, and the chief executive officer (CEO) who had been involved since the organisation was established in 2008. The accident pilot was also the head of aircraft airworthiness and maintenance control for the operator.

Safety management system

At the time of the accident, CASA regulations did not require the operator to have a safety management system (SMS).[41] However, the operator had voluntarily introduced an SMS in 2020.

ICAO defines an SMS as:

A systematic approach to managing safety, including the necessary organizational structures, accountability, responsibilities, policies and procedures. It is designed to continuously improve safety performance through: the identification of hazards, the collection and analysis of safety data and safety information, and the continuous assessment of safety risks. The SMS seeks to proactively mitigate safety risks before they result in aviation accidents and incidents.

The operator’s SMS manual stated:

Risk management incorporates a decision-making process that enables the company to prioritise the reduction or elimination or hazards. This process removes or reduces risk to acceptable levels.

The SMS manual included several sources of information to aid hazard identification such as previous experience, accident investigations, audits, group discussions, and client feedback. The SMS incorporated a hazard register which included various hazards related to the operator’s flight operations, with the chief pilot being responsible for most of them. The register did not include any hazards related to the loss of visual reference, or inadvertent entry of a VFR flight into IMC.

Pilot training

As part of holding a commercial pilot licence (aeroplane), the pilot was required to complete a flight review every 2 years. The review included competencies related to knowledge of pre-flight weather assessment, maintaining situational awareness and decision making, as well as recognising and managing threats and undesired aircraft states. The review required pilots to perform basic flight manoeuvres using full instrument panel, and to recover from upset situations and unusual aircraft attitudes to straight and level flight while operating under simulated IMC. The pilot had successfully completed this review in March 2021. Biennial flight reviews for the commercial pilot licence (helicopter) could also include an instrument flying component but this was optional.

Operator proficiency checks were conducted annually and involved a ground review and flight review, as well as practical and theoretical components on emergencies. The proficiency check did not include any additional training related to instrument flying or VFR‑into‑IMC prevention and recovery, nor was such training required by CASA.

The operator also conducted annual aeronautical decision-making training based on the non‑technical skills theory within CASR Part 61 (flight crew licencing) although it was not required under CASA regulations at the time of the accident.[42] The training had a slightly different syllabus for each recurrent exercise and was intended to be self-paced, with an estimated duration of 2 hours. The subject matter was based on the CASA resource material – Safety behaviours: human factors for pilots: Resource booklet 7 Decision making. The pilot had completed the initial training in September 2020, which required reading the booklet, watching a CASA video on decision making, and completing a short multiple-choice quiz. The first recurrent training was completed in October 2021 and involved similar tasks.

Regulatory oversight

CASA’s surveillance manual outlined that the surveillance program for Authorisation Holders (AH), such as Executive Helicopters, used a systems and risk-based approach to obtain, record, and analyse results to evaluate safety performance. The scheduling of surveillance events was driven by many factors such as external intelligence, outstanding safety findings, time since the last surveillance event, and safety-related risks specific to each AH.

CASA last conducted a surveillance event on the operator in October 2018. That surveillance was classified as ‘Level 1’[43] and conducted on-site at the operator’s premises. The scope of the surveillance included a review of airworthiness assurance, crew scheduling, and flight operations. The surveillance event resulted in 3 findings regarding crew rostering, navigation logs, and operations manual document control.

The operator responded to each finding with satisfactory corrective action and CASA acquitted the 3 findings in January 2019. Another Level 1 scheduled surveillance event was planned for March 2022 but was not conducted as all CASA surveillance events were postponed due to the flight operations regulations transition.

CASA used an Authorisation Holder Performance Indicator (AHPI) tool to assist with surveillance. The AHPI tool was one of a number of factors used to determine the need for surveillance events. The AHPI tool was a questionnaire-based tool consisting of several factors and sub-factors associated with organisational characteristics and performance commonly thought to affect or relate to safety performance behaviour. The assessment would result in the AH being assigned to either category 1 (higher level surveillance focus required) or category 2 (normal surveillance level appropriate). Since January 2019, 3 AHPI assessments had been conducted on Executive Helicopters — in May 2019, May 2020, and November 2021 — with each resulting in the operator being assigned to category 2 indicating that the normal level of surveillance was appropriate.

VFR-into-IMC

Visual flight rules pilots flying into IMC (VFR-into-IMC) has been a worldwide challenge in aviation and continues to represent a significant portion of fatal accidents. VFR-into-IMC accidents usually involve either loss of control, spatial disorientation, or controlled flight into terrain. A significant number of studies have examined VFR‑into-IMC accidents, and a range of factors are usually involved, of which many are related to decision making.

Decision making

Pilot decision making is a cognitive process used to select a course of action between alternatives. Several factors, circumstances, and biases can affect decision making, including the flight objective or goal, and the pilot’s knowledge, experience, and training (Endsley, 1995).

The CASA Resource booklet 7 Decision making contained the following:

In aviation, decision making is involved in every action a pilot makes before and during a flight, including pre-flight activities, and go/no-go decisions. Every decision will, hopefully, ensure an uneventful, safe flight, but the safety consequences of some poor decisions can be irreversible.
For example…A non-instrument rated pilot who proceeds with a flight in marginal weather and ends up in instrument meteorological conditions (IMC) decides to firstly, proceed with the flight and secondly, not turn back when the weather indicated visual flight rules were not able to be maintained.
Pilots frequently face classic ‘go/no-go’ decision making because of ambiguous or dynamically changing conditions. [Airline] pilots receive intensive training in how to make such decisions, with regular refresher training in these skills in a simulator. For a charter pilot, however, without the intensive, practical training in a simulator, it can be very different. They can be faced with a challenging scenario they have not encountered before, or feel pressured to continue a flight despite changing conditions.

Air transport operations in smaller aeroplanes, such as that conducted by the operator, do not have the same sophistication of systems, processes, and procedures as larger airlines (Harris and others, 2022):

Commercial pilots often fly single-pilot, in remote areas, with limited direct supervision, requiring a greater level of decision making autonomy. These challenges can lead to pilots pushing their own and/or operational limits.

Recent research into general aviation pilots involved in the entry of VFR flights into IMC, noted a distinction between intentional and unintentional VFR-into-IMC (Stanton, 2022), which was normally not considered within previous research. Unintentional or inadvertent VFR‑into‑IMC flight were those where there was no deliberate intention to do so and occurred ‘…due to poor situational awareness or poor interpretation of weather cues whilst operating in a dynamic, sometimes subtly changing environment (Orasanu et al., 2001)’.

Intentional flights were those where the pilots were:

…conscious of the adverse weather (and the associated rules) and yet deliberately decide to continue into the poor conditions and have formed a cognitive behavioural intention to do so.
The violation, in this case, is not malevolent; instead, the person's objective is to adapt, gain efficiencies or achieve goals in complex real-world settings. Violations of this nature are not the action of bad apples or those who are acting irrationally. These intentional actions make sense to the pilots at the time, given the information that they have and the beliefs they hold about themselves and the environment.

A systematic review of the available research into VFR-into-IMC accidents, with a focus on commercial pilots and operations where there was intentional continuation of flight into unsuitable conditions, found the following 2 overarching themes, each with associated personal, social and organisational factors (Harris and others, 2022):

  • continuation influence
  • acceptance of risk/normalisation of deviance.

Continuation influence

Research has shown that pilots often continue VFR flights despite deteriorating cues associated with adverse weather conditions. This ‘plan continuation bias’ is an internal pressure or desire to get to the destination and could result from various factors such as previous encounters with IMC or an inability to detect cues of gradually deteriorating conditions while getting closer to the destination.

The ATSB found that the chances of a VFR-into-IMC encounter for general aviation pilots increased until they reached a maximum during the final 20% of the flight distance (ATSB, 2005). This pattern suggested an increasing tendency on the part of pilots to ‘press on’ as they near their goal with a decreasing probability of turning back or diverting as the destination drew closer.

Practical reasons can also play a role, with pilots continuing because the alternative places them in a location with minimal facilities (accommodation, food, communications). Also, the way alternative options are framed can also have an impact (Harris and others, 2022):

When pilots were required to decide between the acceptance of a certain loss (wasting time, losing money, personal hardship, etc.) or risking potential further loss (the chance of having an accident) “the loss frame” vs. framing the decision as a gain, pilots in the loss frame were significantly more likely to elect to continue with the flight.

The presence of passengers or customers on a flight can also directly, or indirectly, place pressure on a pilot to continue the flight, where the pilot does not want to disappoint the passenger(s) and to avoid social disapproval or failure. A review of United States general aviation aircraft accidents between 1990 and 1997 found a significantly greater percentage of VFR‑into‑IMC accident flights carried passengers on board (Goh and Wiegmann, 2001).

At the operator level, pilots can be influenced by time pressures, resource limitations or financial constraints and incentives. An organisation’s safety culture can also affect pilot motivations and decision making. For example, a safety conscious culture could lead to a pilot choosing a safe option (for example, diversion), while a pilot that fears punishment if they divert may lead them to press on into deteriorating weather.

Acceptance of risk/normalisation of deviance

Decision making under uncertainty involves the perception of risk (Harris and others, 2022). Pilots may detect deteriorating weather but perceive the risk of continuing differently based on factors such as personal experience and ability. Pilots that had lower risk perception, or were less risk averse, were more likely to have encountered adverse weather before:

…some pilots may tend to transition into deteriorating weather / IMC deliberately, on the basis that they [are] familiar with or have experienced relatively similar conditions, they perceive the transition into IMC as comparatively less risky, and experience lower levels of anxiety during the encounter.

These findings were supported by another recent study on VFR-into-IMC accidents, where a cycle of repeated and successful VFR-into-IMC encounters could create a pattern of deviation from the rules (Stanton, 2022):

Those pilots who are most at risk are those who mistakenly consider themselves as above average or experts. This cohort is the least likely to have the metacognitive skills required to identify and exit the cycle, driving progressively greater normalised deviance. This cohort of pilots is the most difficult to target for intervention because, according to how they perceive the world, they have already mastered what we want to teach.

This research also found that the perceptions pilots held about what other people, whose opinion they valued, might expect or think about conducting a VFR flight into IMC, and what these people would do in such a situation, was highly influential to forming an intention to conduct VFR flights into IMC (Stanton, 2022).

From an organisational perspective, pilots could become accustomed to risk-taking when instructed to take-off and ‘…see how bad the weather is…’ if it leads to no negative consequences (Harris and others, 2022):

The pilots become accustomed to the risk-taking because that is what’s expected of them. These cultural norms can become the organizational culture and the low organizational safety standards can lead to pilots being willing to take more risks and to reason away risky decisions. The incremental acceptance of progressively lower levels of safety by a group is the definition of the normalization of deviance.
Pilot decision making during the accident flight

The pilot was described as being diligent with weather-related decision making, knowledgeable and experienced with the local terrain surrounding Brisbane. The pilot’s next of kin and a former colleague reported that the pilot always had alternative options in case poor weather was encountered. On 2 separate occasions the pilot had reportedly landed after encountering poor weather, and either waited until the weather cleared, or sought a different method of travel to get to the destination. A review of the ATSB occurrence database did not identify any weather-related occurrences involving the pilot, nor did CASA hold any records of enforcement action taken against the pilot.

In the time leading up to the accident, the pilot was operating the aircraft in regions of elevated terrain at altitudes below the minimum height requirements. While the pilot had substantial experience flying at low level and in mountainous terrain, as well as previous IFR experience, the ATSB was unable to determine whether this previous experience lowered the pilot’s risk perception and influenced the decision to continue the flight.

While the pilot was also described as being very customer focused, a former colleague reported that the pilot never had any urgency to ‘get the job done’ and would not be pressured by anyone to do something they were not comfortable with. On the day of the accident, there was no evidence of schedule-related time pressure for the passengers’ return to Archerfield. Nevertheless, there was insufficient information to determine whether the pilot was under any real or perceived customer-imposed pressure, or self-induced pressure due to the presence of the passengers, to complete the flight.

From an organisational perspective, the accident pilot and the CEO were, for a significant period of time, the only personnel at Executive Helicopters with responsibility and accountability for the safe operation of aircraft. The full-time pilot who was employed by the operator from January 2021 to June 2022 described the CEO as ‘easy going’ with a friendly and open, professional and personal relationship with the accident pilot.

The CEO was not involved in the day to day flying operations of the operator but would receive regular communications from the accident pilot on these matters. The previously‑employed pilot stated that during their time with the organisation they felt 'very comfortable’ with all aspects of operations and did not experience any pressure to complete flights. Based on this information, it was considered unlikely that there was any direct or perceived organisational pressure on the pilot to continue the flight.

Intervention strategies

The commonly documented strategies to avoid entering IMC are appropriate pre-flight preparation and sound decision making. Initial instrument training required for a commercial aeroplane licence, and recurring training as part of biennial flight reviews, can also assist pilots in maintaining aircraft control in IMC and to recover to VMC. Some recent research and information on aspects related to VFR-into-IMC prevention and recovery are outlined below.

Prevention

The dangers of VFR pilots flying into IMC have been recognised for a very long time, yet VFR pilots still fly into deteriorating weather and IMC. Recent research, which applied the ‘theory of planned behaviour’[44] to intentional VFR-into-IMC flights, summarised the historical attempts at preventing these accidents (Stanton, 2022):

The conventional remedy has been to instruct pilots (who care to read the safety journals and magazines) to plan better, pay more attention to the changing weather and to educate pilots more on the potentially tragic outcomes with messages like you have only 178 seconds to live. This approach appears to have achieved little advancement despite the well-intentioned efforts of many.

This research found that pilot’s ‘…beliefs related to the hazardous consequences of conducting VFR flight into IMC (i.e., behavioural beliefs) had limited influence on a pilot’s intentions’ which could explain ‘…why past attempts at intervention have been unsuccessful for so long’.

The research found that the distinction between inadvertent and intentional VFR-into-IMC was likely an important factor when considering intervention strategies:

…there appears limited discussion or application of the interventional distinctions between the intentional and the unintentional cases. Instead, the problem is frequently contemplated simply as a single problem of VFR flights into IMC. The interventions required are likely to be unique between the unintentional and the intentional cases in order to address the respective underlying foundations.

For intentional VFR-into-IMC, the research indicated that ‘…beliefs associated with social pressures and those associated with a pilot’s perception of their skills and ability were the primary influences on behavioural intentions’. The research suggested that intervention strategies be developed by applying behaviour change theories to pilots to alter their beliefs, attitudes, and perceptions. This conclusion was also supported by other research that reviewed VFR-into-IMC from a behavioural economics[45] perspective, which also suggested more comprehensive weather training was required (O’Mahony et al., 2023). The research proposed 3 interventions to facilitate better pilot decision making in the context of VFR-into-IMC:

The first of these is an acceptance by the regulator that the behavioural biases are real and can result in predictable departures from rationality across the spectrum of pilot skill levels and personalities.
Secondly, the educational regime mandated by CASA has a critical role to play. In playing its role, the regime needs to be deeper and more adept at explaining to pilots the psychological factors to which they may fall victim, and we advocate for regulatory intervention to better educate pilots about their own psychology.
Finally, pilots will need better practical (and mandatory) weather training. Currently, the training available to pilots is based around understanding basic weather theory, being able to predict weather using weather-forecasting tools, and understanding the legal requirements of VMC and IMC. As we have shown, environmental literacy often becomes an issue in flight, with pilots struggling to perceive subtle changes in the weather until the weather has deteriorated to dangerous conditions. This practical en route flying training is apt for simulation-based training, a tool which is becoming more common in [general aviation], with the advent of cheaper and more sophisticated software.

IMC recovery

The Cessna R182 pilot’s operating handbook[46] included an emergency procedure for inadvertently entering clouds. The procedure was to execute a standard rate 180° turn using the aircraft’s compass and clock, while maintaining altitude and airspeed.

The 180° turn may not be suitable for all IMC recovery situations and execution of this turn at low altitude has resulted in controlled flight into terrain (CFIT) accidents or a loss of control during the turn. A 2021 United States General Aviation Joint Steering Committee[47] (GAJSC) report into CFIT accidents recommended a task force be created to review IMC recovery events to ‘…make recommendations on revisiting how we teach and train the [IMC] escape response [manoeuvre] to include an initial climb before any heading change, should the data support such a change.’ An Aircraft Owners and Pilots Association (AOPA) article indicated that climbing, rather than turning, was a valid option to consider depending on the situation faced by a pilot:

For years, student pilots have received three hours of training on flight by reference to instruments with the intent that this training will help them get out of the VFR into IMC trap. The 180-degree turn is normally taught as the escape maneuver, and is often the best option. But there are alternatives to consider.
Reviewing two recent VFR into IMC reports, both pilots opted to climb instead of turning around. In one case, the pilot got a low-altitude warning from an aviation app on a mobile device after losing all outside visual references. The pilot climbed to 3,500 feet and continued along the route of flight until finally exiting IMC some 34 miles later. In the other case, the pilot was in a precarious low-altitude VFR into IMC situation where the aircraft was dodging communication towers and entered a cloud. After momentarily experiencing spatial disorientation, the pilot was able to level the aircraft and then began a climb to altitude into the clouds. After a few minutes the airplane broke into clear skies and the pilot continued to the destination VFR.
In both situations the pilots made the decision to climb to avoid a low-altitude encounter with an object. Both pilots maintained straight-ahead, wings-level climbs and did not deviate from their headings. The attitude indicator was the primary instrument for establishing and maintaining the climb, and the other instruments provided supporting information to confirm that climb. Both pilots deliberately focused on the instruments and did not attempt to look outside, to avoid distraction that can cause spatial disorientation.

Instrument training and flying, such as that conducted during flight reviews can assist in maintaining aircraft control and to recover to VMC conditions, although there are limitations to this approach (AOPA, 2022):

In training, you’re instantly put into an IMC scenario. But it’s slightly deteriorating weather, slowly evolving and enveloping you and your airplane, that lures you into the trap.

To resolve this limitation, the 2021 GAJSC report recommended ‘…to improve scenario-based training through the use of [available] advanced view-limiting device technology that simulates inadvertent IMC entry and/or through the use of flight simulators.’

Related Occurrences

Many similar occurrences have been summarised in the ATSB research report Accidents involving Visual Flight Rules pilots in Instrument Meteorological Conditions as well as in ATSB accident reports, including AO‑2018‑078.

Safety analysis

Introduction

At 0715 local time on 29 August 2022, a Cessna R182 Skylane RG (R182), registered VH-EHM, and operated by Executive Helicopters, departed a private property (Lighthouse) north-east of Roma, Queensland for an air transport flight under visual flight rules (VFR) to Archerfield Airport, Queensland. The aircraft departed with the pilot, 2 passengers, and a passenger’s pet dog on board.

As the aircraft was crossing the elevated terrain of the Great Dividing Range, the pilot encountered forecast low cloud and reduced visibility, and was unable to find a way across that was clear of cloud. With limited fuel remaining, the pilot diverted to Dalby Airport and refuelled the aircraft before departing once again. About an hour later, the aircraft collided with terrain in the D’Aguilar Range about 36 km north-west of Archerfield. All occupants of the aircraft were fatally injured.

The ATSB did not identify any aircraft defects or anomalies that may have contributed to the accident. As such, the following analysis will examine the:

  • pilot’s pre‑flight planning and decision making.
  • continuation of the flight into adverse weather.
  • operator’s risk management.
  • search and rescue aspects.

Pre-flight planning and diversion to Dalby

Pre-flight weather assessment

While at Lighthouse, the forecast weather at the destination (Archerfield) was suitable for a VFR arrival. However, the en route forecast predicted low cloud, rain, fog and associated reduced visibility, particularly around the elevated terrain of the Great Dividing Range, with cloud down to ground level in some areas. Although the forecast predicted acceptable visibility below the cloud layers, the weather conditions around the elevated terrain of the range – which had to be crossed to reach Archerfield – were unsuitable for visual flight.

About 6 minutes before the flight departed Lighthouse, the pilot requested weather information through the National Aeronautical Information Processing System (NAIPS). This was the pilot’s first NAIPS weather request since their departure from Archerfield the previous day. The exact weather information reviewed by the pilot could not be determined, nor is it not known whether the pilot accessed other non‑approved sources of weather. Nevertheless, the information available as part of the NAIPS request was sufficient for the pilot to assess the weather en route and to inform the pilot’s pre-flight decision making. However, the minimal time between the NAIPS weather request and subsequent take-off (6 minutes), provided limited opportunity for a thorough review of the en route weather and was consistent with a strong motivation to conduct the flight despite the forecast weather conditions.

Fuel planning

Although fuel was available at Lighthouse, and there was sufficient fuel on-board to complete the flight in ideal conditions, there was insufficient fuel to account for weather-related diversions or meet contingency fuel requirements. Furthermore, depending on the fuel flow data used for the calculations, there was also insufficient final reserve fuel on-board.

The limited pre-flight planning information available meant that the investigation was unable to determine the factors considered by the pilot with respect to fuel planning prior to departure.

Flight notification and search and rescue

Civil Aviation Safety Regulations (CASR) required that, before undertaking the flight, the pilot leave details of the flight and arrival time with a ‘responsible person’ who knew when and how to contact the Joint Rescue Coordination Centre (JRCC) and would do so if the flight was overdue.

The operator's documented procedures reflected this requirement and stipulated that this ‘responsible person’ could be someone from the operator or a representative of a client onboard.

The operator reported that the pilot did not always follow this documented procedure and would sometimes provide flight details to a family member, as occurred on the accident flight. Providing the flight note to this family member was still sufficient to meet the regulatory requirement if they were aware of their obligations and expected actions. However, the investigation identified various deficiencies in relation to the pilot’s compliance with this requirement for the accident flight:

  • The family member was notified about 30 minutes after departure from Lighthouse, limiting search and rescue (SAR) functions during that initial part of the flight.
  • An unspecific arrival time of ‘late morning’ was provided which was not suitable for the purposes of timely SAR action.
  • Although the flight diverted to Dalby, the pilot did not notify the family member when there was a change to the flight route and arrival timing.
  • The pilot had not briefed the family member about the correct actions to take for an overdue flight, resulting in a delay of over 2 hours in notifying the operator that the flight was overdue. This substantially delayed the subsequent emergency SAR response and potential medical attention (in the event of a survivable accident).

The accident was non-survivable, and consequently, a timely SAR response and immediate medical aid would not have altered the outcome. However, in different circumstances, SAR notification and the carriage and use of manually activated emergency beacons would likely have played a key role in increasing the chances of post‑accident survival by facilitating rapid medical aid to treat injuries.  

Departure and diversion to Dalby

While the forecast indicated that visual meteorological conditions (VMC) would probably not be maintained while transiting the elevated terrain of the Great Dividing Range, the decision to depart Lighthouse towards Archerfield was in itself reasonable. With adequate fuel on-board and escape routes planned, actual weather conditions could be assessed and managed in‑flight. However, doing so placed additional pressure on the pilot’s in‑flight decision making capabilities.

After encountering the forecast cloud, the pilot continued to manoeuvre to try to find a way through the Great Dividing Range with the aircraft’s fuel running low. The pilot then diverted to Dalby, landing with less than the required final reserve fuel. Although this may have been influenced in part by the aircraft being equipped with instrumentation capable of indicating the fuel state accurately, this indicated that the pilot’s planning before and during the flight was ineffective, and there was likely a motivation to complete the flight even though reduced safety margins existed.

Summary

The operator’s small size, limited flight operation personnel, and single-pilot operations, required the accident pilot to exercise a high level of pre-flight and in-flight decision-making autonomy.

The decision to depart into forecast weather that was not conducive to visual flight, with limited time for pre-flight weather review, insufficient required fuel on-board, and without an appropriate flight notification system, combined to reduce safety margins and presented an increased risk to occupants on board.

Although not contributory to the accident outcome, these factors were indicative of inadequate pre-flight planning. However, having attempted to cross the Great Dividing Range, the pilot did make an effective in-flight decision to return to Dalby to refuel. This provided an opportunity to re‑assess the weather and its suitability for continued flight, as well as providing an opportunity to identify alternative options for the passengers’ continued travel.

Departure from Dalby and continuation of flight

Pre-flight

The updated weather forecast information available to the pilot while at Dalby, predicted en route weather conditions similar to those already experienced but the forecast cloud between 1,500‑2,500 ft was expected to start dissipating within about 2 hours (by 1100), and clear completely by 1200. Also, the forecast deteriorating weather conditions with reduced visibility and low cloud cover at Amberley and Archerfield were also expected to clear by 1100. These deteriorating periods had forecast conditions that were less than the VMC criteria necessary to achieve the minimum height of 1,000 ft AGL required to transit Amberley and land at Archerfield. However, the conditions were within the special VFR criteria which meant that a transit and landing could have been possible had the pilot requested a special VFR clearance from air traffic control at Amberley and Archerfield.

As was the case before departing Lighthouse, although good visibility below the cloud layers was forecast en route, conditions around the elevated terrain of the Great Dividing Range were not suitable for visual flight.

The pilot spent about 10 minutes on the ground at Dalby, almost all of which was spent refuelling, and there were no NAIPS logins recorded during time on the ground. Therefore, it was unlikely that the pilot reviewed the updated forecast either from NAIPS or another source before take-off (for example, via radio), although the pilot likely reviewed it in-flight, shortly after take-off. This suggested that there was little consideration given to alternative means of getting the passengers to their destination (for example, ground transport or waiting until the weather improved as was forecast to occur within the next 2-3 hours). The short time spent on the ground provided further evidence of a motivation to complete the flight despite having already encountered the forecast cloud in-flight.

After departure

Across the Great Dividing Range

The flight track showed that, following departure from Dalby, the pilot attempted to find a different path across a section of the Great Dividing Range to get to the low-lying terrain west of Amberley, this time tracking south of Toowoomba. The pilot requested updated weather through NAIPS about 13 minutes after take-off. However, re-assessing the weather in‑flight removed the ability of the pilot to decide against taking off again. Research indicates that continuing with an initial plan or strategy despite indications that an alternative course of action may be safer can be stronger after take-off, making the decision to discontinue the flight more difficult.

The forecast and observed weather conditions, as well as the pilot’s flight track, indicated that a cloud layer was obscuring terrain on Main Range. The pilot’s first attempt to cross this range was unsuccessful, likely due to cloud, with a 180° turn performed to try to cross at a different location. The pilot then tracked south-east and between 2 peaks at low level, before heading down a long valley towards low-lying coastal terrain.

The flight track suggested familiarity and knowledge of the terrain with the pilot possibly heading towards known locations that presented the best chance of transit. However, the aircraft crossed over the terrain with minimal separation. This was likely indicative of the pilot’s intention and motivation to continue and complete the flight, despite the forecast and observed weather conditions.

Amberley and surrounding area

After crossing Main Range, the pilot descended the aircraft towards Gatton before tracking towards Lowood, following the low-lying terrain below cloud. Weather observations from Gatton, Amberley, and Lowood Golf Course indicated a low cloud base but with good visibility below the layer. However, a weather report about 15 minutes after the accident indicated the forecast deteriorating weather at Amberley had reduced the observed visibility to 4,000 m and lowered the scattered cloud to 700 ft. These conditions would have meant that the area was not suitable for visual flight at that time.

Lake Manchester VFR route

The Lake Manchester VFR route, intended to be used in VMC, had narrow lateral and vertical separation between the hilly terrain of the adjacent D’Aguilar Range and controlled airspace, which increased the difficulty of this route in poor weather. The flight track indicated that the pilot was trying to follow the route to get to Archerfield. However, the adjacent range was obscured by cloud, so it was likely difficult to orientate the aircraft with identifiable ground features to assist with navigation. In addition, the aircraft’s relatively high speed for the conditions reduced the time available for decision making.

After turning east over Fernvale, the aircraft tracked towards a mountain at an altitude below its peak before conducting another 180° turn at about 1,200 ft and less than 2 km from rising terrain. About 10 seconds later, the pilot conducted a right turn at about 140 kt ground speed towards the rising terrain of the D’Aguilar Range, which had low cloud cover obscuring some of the peaks, and shortly after, impacted terrain.

Evidence from the site of the accident and the sound of the aircraft up until the impact indicated:

  • no abnormal engine or propeller sounds up to the time of impact
  • no pre-impact issues with the aircraft, engine, or propeller
  • a relatively high-speed impact
  • a shallow descent at the time of impact with the trees and terrain
  • an angle of bank at the time of impact similar to previous turns completed during the flight.

As a result, the ATSB concluded that the aircraft was likely under control during the impact with the pilot very likely unaware of the aircraft’s proximity to the terrain. Although the pilot was knowledgeable and experienced with the location of the D’Aguilar Range relative to Fernvale, the low cloud over the range and the flight track indicated the aircraft was very likely in instrument meteorological conditions (IMC) in the final stages of the flight. The pilot very likely lost visual reference with the ground, limiting the ability to geographically orient themselves and avoid the surrounding hills, eventually leading to a controlled flight into terrain. The high speed would also have limited the pilot’s ability to react and avoid any terrain identified in the final moments of the flight.  

Pilot decision making

On the day of the accident, the pilot was conscious of the adverse weather forecast and encountered during the flight prior to landing at Dalby. The pilot then made a deliberate decision to depart Dalby and continue the flight into known unsuitable weather conditions at cruise speed, low altitude, and towards a known area of rising terrain obscured by cloud. This was inconsistent with the prudent judgement, behaviour and decision making capability attributed to them by others. Nevertheless, the available information suggests the pilot was probably influenced by plan continuation bias – an internal pressure or desire to get to the destination – to continue the flight, which probably became stronger as they got closer to Archerfield Airport. However, due to a lack of information, the ATSB was unable to conclusively determine the pilot’s motivations in choosing to continue the flight in unsuitable circumstances with reduced safety margins.

Operator risk management

Although inadvertent IMC was a well-known, high consequence risk, the operator's hazard and risk register, which formed part of the organisation's safety management system (SMS), did not identify this hazard. Consequently, there was no specific assessment of its risk to operations and no specific risk mitigation in place.

Although not documented in the operator’s SMS, the risk of inadvertent IMC was being managed by requiring that pilots not commence flights unless VFR conditions were forecast for the route and at the destination, and to monitor and plan alternative actions in-flight if weather deteriorated. In this accident, the pilot did not follow these procedural controls. The controls relied on an individual pilot’s pre-flight assessment of weather, and on in-flight weather-related decision making, neither of which were addressed by the operator through any specific training, procedures, or review.

In addition, the operator did not have any procedures or training in place beyond the minimum regulatory instrument flying component of fixed wing flight reviews for pilots to recover from an inadvertent IMC encounter. Historically, relying on pilots to avoid IMC has been the primary strategy in preventing inadvertent IMC accidents. However, the continuing occurrence of these accidents demonstrates that this strategy alone is insufficient.

As the hazard of inadvertent entry into IMC was not identified in the risk register, no conclusions could be drawn about the nature and effectiveness of the specific risk controls that might have been implemented, nor whether the pilot would have utilised them. Therefore, while important, the absence of the hazard being identified in the operator’s SMS was not considered contributory to the accident.

On-board recording devices

There was no regulatory requirement for the aircraft to be fitted with on-board recording devices. However, this and numerous other investigations have shown that the lack of such devices limits the ability to understand and determine all of the factors that contributed to an accident. In turn, important safety issues that present a hazard to current and future operations were potentially not identified. Conversely, other investigations where some form of recording device was on board, provided valuable information regarding the accident.

In this investigation, flight track data was available to identify the aircraft’s movement. However, the ATSB was unable to determine why a highly experienced commercial pilot continued the flight into a known area of high terrain obscured by cloud, nor could the circumstances of what was occurring in the cockpit, especially in the final minutes before the accident, be determined. Recorded information may have provided some insights into the pilot’s decision making during the flight and further detail on how the accident developed.

The use of lightweight recorders on smaller aircraft conducting commercial operations has the potential to provide a relatively simple and cost-effective way of achieving many of the benefits that are provided by traditional recorders fitted to larger aircraft.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. 

Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the VFR into IMC and controlled flight into terrain involving Cessna R182, VH-EHM, 36 km north-west of Archerfield Airport, Queensland on 29 August 2022

Contributing factors

  • After encountering and manoeuvring around forecast low cloud, insufficient fuel remained on board the aircraft to complete the flight and the pilot diverted to Dalby to refuel. After refuelling, the pilot departed toward forecast en route weather unsuitable for visual flight.
  • The pilot continued the flight at low level, at cruise speed, into weather conditions unsuitable for visual flight. This very likely resulted in the pilot experiencing a loss of visual reference leading to controlled flight into terrain.

Other factors that increased risk

  • Although in this instance the accident was not survivable, several deficiencies were identified that delayed a search and rescue response:
    • Contrary to operator procedures, the pilot provided flight notification information to a family member not associated with the operator.
    • The family member was not provided with any information on appropriate actions to be taken in the event of the aircraft being overdue.
    • The pilot provided flight notification information to the family member about 30 minutes after take-off from Lighthouse which limited search and rescue functions for that time.
  • The aircraft likely departed Lighthouse for the flight to Archerfield Airport with insufficient fuel to account for weather-related diversions and the required contingency and final reserve fuel.
  • The operator's hazard and risk register, which formed part of the organisation's safety management system, did not identify inadvertent entry into instrument meteorological conditions as a hazard, which reduced the ability of the organisation to effectively manage the related risk. (Safety issue)

Other findings

  • While flight tracking data was available, the aircraft was not fitted with an onboard recording device. This could have provided valuable information to better understand the pilot’s in-flight weather-related decision making.

Safety issues and actions

Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.

Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.

All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.

Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.

Operator risk management

Safety issue number: AO-2022-041-SI-01

Safety issue description: The operator's hazard and risk register, which formed part of the organisation's safety management system, did not identify inadvertent entry into instrument meteorological conditions as a hazard, which reduced the ability of the organisation to effectively manage the related risk.

Glossary

AGLAbove ground level
AMSLAbove mean sea level
AOCAir Operator's Certificate
AOPAAircraft Owners and Pilots Association
ATCAir traffic control
CASACivil Aviation Safety Authority
CASRCivil Aviation Safety Regulations
CEOChief Executive Officer
CoACertificate of airworthiness
CFITControlled flight into terrain
CTAControl area
CTRControl zone
DAMEDesignated aviation medical examiner
ELTEmergency locator transmitter
EPIRBEmergency position indicating radio beacon
GAFGraphical area forecast
GAJSCGeneral Aviation Joint Steering Committee 
HOFOHead of flying operations
ICAOInternational Civil Aviation Organization
IFRInstrument flight rules
IMCInstrument meteorological conditions
ISAInternational Standard Atmosphere
JRCCJoint Rescue Coordination Centre
NAIPSNational Aeronautical Information Processing System
PLBPersonal locator beacon
POHPilot’s operating handbook
SARSearch and rescue
SMSSafety management system
TAFTerminal area forecast
TASTrue Airspeed
TAWSTerrain awareness and warning system
VFRVisual flight rules
VMCVisual meteorological conditions

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilot’s next of kin and former colleagues
  • the passengers’ friends and colleagues
  • Bureau of Meteorology
  • Geoscience Australia
  • Airservices Australia
  • Executive Helicopters (operator)
  • Civil Aviation Safety Authority
  • OzRunways
  • Avdata
  • Fernvale Rural Fire Brigade
  • Queensland Police Service
  • witnesses
  • CCTV video footage of weather near the aircraft’s flight path.

References

Australian Transport Safety Bureau. (2005). General Aviation Pilot Behaviours in the Face of Adverse Weather. B2005/0127

Australian Transport Safety Bureau. (2013). A review of the effectiveness of emergency locator transmitters in aviation accidents.

AR-2012-128 (2.51 MB)

Australian Transport Safety Bureau. (2019). Avoidable Accidents No. 4: Accidents involving Visual Flight Rules pilots in Instrument Meteorological Conditions. AR-2011-050

Australian Transport Safety Bureau. (2021). Collision with water involving de Havilland Canada DHC-2, VH-NOO. AO-2017-118

Australian Transport Safety Bureau. (2021). VFR into IMC and controlled flight into terrain involving Pilatus Britten-Norman BN2A, VH-OBL. AO‑2018‑078

Australian Transport Safety Bureau. (2023). VFR into IMC, loss of control and collision with terrain involving Airbus Helicopters EC130 T2, VH-XWD. AO-2022-016

Civil Aviation Safety Authority. (2019). Safety behaviours: human factors for pilots: Resource booklet 7 Decision making (2nd edition)

Collins, J. (2022). Training and Safety Tip: Escaping the VFR-into-IMC Trap. Aircraft Owners and Pilots Association (AOPA).

Endsley M.R. (1995). Toward a theory of situation awareness in dynamic systems. Human Factors, Volume 37, No. 1, 32-64

Federal Aviation Administration. (2023). Information for Operators (InFO): Terrain Awareness and Warning Systems (TAWS) Nuisance Alerts

General Aviation Joint Steering Committee (GAJSC). (2021). Controlled Flight Into Terrain (CFIT) Working Group

General Aviation Joint Steering Committee (GAJSC). (2021). Controlled Flight Into Terrain (CFIT) Working Group: Appendix 6 — Detailed Implementation Plans for Safety Enhancements

Harris M.R., Fein E.C. and Machin M.A. (2022). A Systematic Review of Multilevel Influenced Risk-Taking in Helicopter and Small Airplane Normal Operations. Front. Public Health 10:823276. doi: 10.3389/fpubh.2022.823276

International Civil Aviation Organization. (2018). Safety Management Manual (4th ed). ICAO Doc 9859, Montreal

O'Mahony et al. (2023). VFR Into IMC Through the Lens of Behavioral Economics. Journal of Air Law and Commerce. Volume 88, Issue 1, Article 4 https://scholar.smu.edu/jalc/vol88/iss1/4

Smith, M. (2022). 178 Seconds: VFR into IMC is an Insidious Trap. Aircraft Owners and Pilots Association (AOPA)

Stanton A. (2022). 'Gathering Clouds' A Study of Plan Continuation, Risk, Rules, and Pilot Behaviour. https://doi.org/10.25904/1912/4844

Wilson, D.R., & Sloan, T.A. (2003). VFR Flight Into IMC: Reducing the Hazard. Journal of Aviation/ Aerospace Education & Research, 13(1). https://doi.org/10.15394/jaaer.2003.1567

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the aircraft operator and the Civil Aviation Safety Authority.

A submission was received from the aircraft’s operator.

The submission was reviewed and, where considered appropriate, the text of the report was amended accordingly.

Appendices

Appendix – Fuel calculations

Background

An assessment was undertaken to determine the likely quantity of fuel on-board the aircraft when it departed Lighthouse, and if that quantity was sufficient for the intended flight to Archerfield.

Calculations – Fuel on-board at Lighthouse

Using the maximum capacity of the fuel tanks and the fuel uplift data at Dalby, the useable fuel remaining in the tanks on landing at Dalby could be calculated (20.7 L). The total fuel used during the flight (taxi, climb, and cruise) from Lighthouse to Dalby was estimated using the pilot’s operating handbook (POH),[48] the operator’s operations manual, and the forecast weather.

Taxi

Total taxi fuel was calculated from the POH as the difference between the maximum ramp weight (1,411.6 kg) and maximum take-off weight (1,406.1 kg). The operator’s operations manual also provided an estimated taxi fuel amount.

Climb

Climb fuel consumption rate data in the POH was available for maximum aircraft weight, and International Standard Atmosphere (ISA) conditions and for normal climb performance. Similar temperature conditions to International Standard atmosphere (ISA) were forecast. The main cruise altitude from the aircraft’s OzRunways flight track data was 3,400 ft between Lighthouse and Dalby. The POH data provided fuel consumption for 3,000 ft and 4,000 ft so an interpolation calculation was conducted.

Cruise

Fuel consumption from Lighthouse to Dalby was calculated using data provided in the POH, operator’s operations manual, and forecast weather. As the cruise power setting for the flight was not known, cruise fuel consumption rates were calculated for 3 common engine power settings (75%, 65% and 55%). The POH data assumed maximum take-off weight and standard ISA conditions. The most relevant data for the 3,400 ft cruise altitude was contained in the performance chart for 4,000 ft altitude. For calculations conducted using the operations manual data, the provided ‘block fuel flow’ was used as the cruise and climb fuel flow.

Cruise time was based on the OzRunways flight track data after reaching cruise level until landing at Dalby. Although about two-thirds of the flight was at a similar cruise altitude, the remaining third was made up of 2 climbs and 2 descents along with heading changes. It was assumed that the fuel consumption rate during these phases averaged out to be similar to the cruise fuel consumption rate (since a higher fuel consumption rate would occur during climb with a lower rate during descent). Therefore, the cruise fuel consumption rate was used for the flight time between initially reaching cruise altitude and landing at Dalby.

The actual weight of the aircraft at the same power level and operating altitude can affect the cruise speed of the aircraft and thus flight time and total fuel consumption. POH fuel consumption and related true airspeed (TAS) data was provided at maximum weight but the aircraft during the flight was below this weight. The estimated aircraft departure weight based on the operations manual fuel usage was about 1,269 kg. However, the difference in TAS at this weight was considered minimal so no correction to the cruise time was applied.

The estimated fuel on-board at Lighthouse for each scenario is shown in Table 2.

Table 2: Estimated fuel on-board VH-EHM at Lighthouse

Table 2: Estimated fuel on-board VH-EHM at Lighthouse
Calculations – Fuel required from Lighthouse to Archerfield

The Civil Aviation Safety Regulations defined the fuel requirements for Part 135 operators. The following fuel was required for a Part 135 flight:

  • taxi fuel – fuel used before take-off
  • trip fuel – fuel for take-off, climb, cruise, descent, and landing
  • contingency fuel – 10% of trip fuel for a piston engine aeroplane to compensate for unforeseen factors
  • final reserve fuel – 45 minutes flight time for a piston engine aeroplane and is useable fuel remaining on completion of final landing at the aerodrome
  • Destination alternate fuel (if required)
  • Holding fuel (if required)
  • Additional fuel (if required)

An estimate on the fuel required to complete the flight from Lighthouse to Archerfield (taxi, climb, cruise) was determined using data available in the POH, operations manual and the forecast wind conditions.

The anticipated ground speed was calculated based on the TAS and forecast wind conditions. The Bureau of Meteorology grid point wind and temperature chart forecast 13‑21 kt wind from 70° at 2,000 ft and 14-20 kt wind from 50-80° at 5,000 ft for most of the planned flight which was on a 115° track. Therefore, an estimated 10 kt headwind was used for the calculations. For the different power settings, the ground speed was used along with the cruise distance to determine the total time and fuel consumption during cruise. For the operations manual fuel flow calculations, the total planned distance to Archerfield was used as the ‘block fuel flow’ accounted for climb, cruise, and descent fuel consumption.

Cruise fuel planning was conducted to overhead the destination aerodrome at cruise level. Manoeuvring and approach fuel consumption was not considered.

Contingency fuel

Contingency fuel was 10% of the calculated trip fuel.

Final reserve fuel

Final reserve fuel was 45 minutes at holding speed, ISA conditions and 1,500 ft. The POH provided a holding fuel of 23.8 L based on 45 minutes at 45 % engine power. The operations manual provided an expected ‘holding’ fuel flow of 40 L per hour (30 L for 45 mins).

Destination alternate fuel, holding fuel, and additional fuel

Either the ‘destination alternate fuel’ or ‘holding fuel’ was required if the destination forecast was below the alternate minima. The relevant Terminal Area Forecast (TAF) for Archerfield forecast conditions above the alternative minima, so no holding or destination alternate fuel was required for the flight. ‘Additional fuel’ was only required for multi-engine aircraft, or aircraft with pressurisation. Since VH‑EHM was a single-engine non-pressurised aircraft, ‘additional fuel’ was not required. The results are shown below in Table 3.

Table 3: Estimated minimum regulatory fuel required for planned flight to Archerfield

Table 3: Estimated minimum regulatory fuel required for planned flight to Archerfield
Estimated fuel margin

The results of the above calculations are shown below in Table 4 to determine the fuel margin between the useable fuel on-board and the minimum required fuel.

Table 4: Estimated fuel margin for the planned flight to Archerfield

Table 4: Estimated fuel margin for the planned flight to Archerfield

The results are based on forecast ideal weather conditions. As per the general fuel requirements in the CASR, in determining the quantity of useable fuel required, the pilot in command must also consider the effect of relevant meteorological reports and forecasts.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2023

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.


[1] The flight was operated under Civil Aviation Safety Regulations Part 135 (Air transport operations – smaller aeroplanes).

[2] Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to fly the aircraft while maintaining visual separation from terrain and other aircraft.

[3] GPS altitude from OzRunways, which is truncated to 100 ft increments.

[4] Data used for terrain elevation does not account for vegetation or structures such as power lines, which may protrude some distance above the ground.

[5] Before the introduction of the Civil Aviation Safety Authority (CASA) Part 61 licencing regulations in 2014, under Civil Aviation Regulation 5, pilots maintained instrument currency by completing an instrument ‘renewal’. Under Part 61, pilots maintained this currency by completing an ‘instrument proficiency check’.

[6] A low-level (LL) rating is needed for a low-level flight operation (below 500 feet AGL including low-level aerobatics).

[7] Aerial stock mustering involving the direct use of aircraft for the movement of livestock.

[8] Instrument flight rules (IFR): a set of regulations that permit the pilot to operate an aircraft in instrument meteorological conditions (IMC), which have much lower weather minimums than visual flight rules (VFR). Procedures and training are significantly more complex as a pilot must demonstrate competency in IMC conditions while controlling the aircraft solely by reference to instruments. IFR-capable aircraft have greater equipment and maintenance requirements.

[9] An aircraft’s maintenance release is a document that provides registered operators and pilots with evidence that an aircraft has had the required maintenance carried out, provides details of any defects that may require rectification before a flight can commence, and also provides essential information about any scheduled maintenance actions that may become due before completion of a planned flight.

[10] Global Navigation Satellite System: A satellite-based radio navigation system that uses signals from orbiting satellites to determine precise position and time.

[11] A TAWS provides visual and aural alerting including a look-ahead terrain function. TAWS is a generic term that also includes a ground proximity warning system (GPWS) with a forward-looking terrain avoidance function. A TAWS is an important tool to help minimise the risk of controlled flight into terrain (CFIT). It provides an independent and unambiguous warning of proximity to the ground or obstacles, regardless of any navigational uncertainty or error such as mis-setting or misreading the altimeter.

[12] The series of Technical Standard Orders (TSO) C151 stipulated the minimum operational performance standards that a terrain awareness and warning system (TAWS) must meet to comply with regulatory requirements for the fitment and use of those systems.

[13] Federal Aviation Administration, 2023, Information for Operators (InFO) - Terrain Awareness and Warning Systems (TAWS) Nuisance Alerts.

[14] Spidertracks is a subscription aircraft monitoring service that allows operators to track and monitor the location of aircraft at regular intervals. The location is recorded and transmitted by a unit that is fitted to the aircraft.

[15] CASR Part 91 Manual of Standards (MoS), section 7.02.

[16] The National Aeronautical Information Processing System (NAIPS) is a computerised, aeronautical information system. It processes and stores meteorological and NOTAM information as well as enables the provision of briefing products and services to pilots.

[17] A Terminal Area Forecast (TAF) is a statement of meteorological conditions expected for a specified period in the airspace within a radius of 5 NM of the aerodrome reference point.

[18] METAR: a routine aerodrome weather report issued at routine times, hourly or half-hourly.

[19] All cloud heights stated are AMSL.

[20] Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘few’ indicates that up to a quarter of the sky is covered, ‘scattered’ indicates that cloud is covering between a quarter and a half of the sky, ‘broken’ indicates that more than half to almost all the sky is covered, and ‘overcast’ indicates that all the sky is covered.

[21] INTER: an intermittent deterioration in the forecast weather conditions, during which a significant variation in prevailing conditions is expected to last for periods of less than 30 minutes duration.

[22] The timestamp on the video footage was likely accurate within minutes based on comparison with other sources. In any event, the weather conditions shown in the video footage were similar for at least 15 minutes before and after the recorded accident time.

[23] CASR Part 91, Table 2.07 (3).

[24] CASR 135.230.

[25] Instrument meteorological conditions (IMC): weather conditions that require pilots to fly primarily by reference to instruments, and therefore under Instrument Flight Rules (IFR), rather than by outside visual reference. Typically, this means flying in cloud or limited visibility.

[26] CASR 91.265 and 91.267.

[27] OzRunways is an electronic flight bag application that provides navigation, weather, area briefings and other flight information. It provides the option for live flight tracking by transmitting the device’s position and altitude.

[28] A common traffic advisory frequency is a designated frequency on which pilots make positional broadcasts when operating in the vicinity of a non-controlled airport, or within a broadcast area.

[29] The height above ground level was based on GPS altitude available from OzRunways (truncated to 100 ft increments), and Geoscience Australia terrain elevation data.

[30] QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean sea level.

[31] CASR Part 135 Manual of Standards (MoS), section 11.51.

[32] The force needed to accelerate a mass. G-force is normally expressed in multiples of gravitational acceleration (normal gravity = 1g).

[33] CASR Part 91 Manual of Standards (MoS), section 9.02.

[34] SARTIME: An abbreviation for ‘time search action required’. A SARTIME is the time nominated by a pilot for the initiation of Search and Rescue (SAR) action.

[35] Flight Note: Details of the route and timing of a proposed flight provided by the pilot in command of an aircraft, other than notification submitted to Airservices Australia, and which is required to be left with a person who could be expected to notify appropriate authorities in the event that the flight becomes overdue.

[36] Automatic Dependent Surveillance - Broadcast (ADS-B) is a system in which equipment on board an aircraft automatically broadcasts the precise location of the aircraft. The data can be used by other aircraft and air traffic control to identify the aircraft’s position and altitude without the need for radar.

[37] CASR Part 135 Manual of Standards (MoS), chapter 7.

[38] The Pilots Operating Handbook provided a value of about 24 L compared with 30 L from the operator’s operations manual.

[39] A notice distributed by means of telecommunication containing information concerning the establishment, condition or change in any aeronautical facility, service, procedure or hazard, the timely knowledge of which is essential to personnel concerned with flight operations.

[40] The AOC was issued before the CASA flight operation rules changed in December 2021, where the term ‘air transport’ replaced charter, regular public transport, and air ambulance when conducted for hire or reward.

[41] The operator was required to have a CASA-approved SMS by December 2024.

[42] The operator will be required to have a CASA approved program for training and assessing operational safety‑critical personnel in human factors principles and non‑technical skills by a future date to be specified by CASA.

[43] A structured, forward-planned, larger-type, surveillance event, which examined an authorisation holder’s systems, safety risk controls, and processes.

[44] The theory of planned behaviour posits that the most immediate cognitive antecedent to performing a distinct behaviour is the formation of an intention. The theory suggests that behavioural intentions are formed and can be predicted, predominantly from just 3 kinds of beliefs that a person holds in relation to the behaviour: attitude toward the behaviour, social norms, and perceived behavioural control (Stanton, 2022).

[45] Economics has traditionally assumed people always make decisions in their best interests. Behavioural economics challenges this view by providing a more realistic model of human behaviour. It recognises we are systematically biased (for example, we tend to satisfy our present self rather than planning for the future) and can make decisions that conflict with our own interests.

[46] The pilot’s operating handbook (POH) for the aircraft could not be located. Information from the POH of another Cessna R182 Skylane RG with a different serial number was used.

[47] The General Aviation Joint Steering Committee (GAJSC) is a United States based public-private partnership focused on improving the safety of the general aviation industry.

[48] As the aircraft’s POH was damaged during the accident, the POH for a different, but similar, 1978 Cessna R182 Skylane RG aircraft was used (serial number R18200450). The performance related data should be similar or identical to the data for VH-EHM.

Preliminary report

Report release date: 19/12/2022

This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

The occurrence

At 1055 local time on 28 August 2022, a Cessna R182 Skylane RG (R182), registered VH-EHM (EHM) and operated by Executive Helicopters, departed Archerfield Airport, Queensland, for an air transport[1] flight under visual flight rules (VFR)[2] to a private property north‑east of Roma, Queensland. The aircraft departed with the pilot and 2 passengers. The aircraft landed at about 1230 and the occupants spent the night at the property.

At 0715 on the following day, the pilot and 2 passengers departed from the property in EHM for a VFR return flight back to Archerfield (Figure 1). Recorded flight tracking data showed the aircraft was initially established on a direct south‑easterly track towards Archerfield at cruise altitudes of between 3,400 ft and 3,900 ft above mean sea level (AMSL). The weather forecast available from the Bureau of Meteorology (BoM) at the time of departure indicated that the route to Archerfield could be affected by low cloud, rain, fog and associated reduced visibility.

At 0828, the aircraft turned left and descended to about 1,800 ft AMSL – 600 ft above ground level (AGL). The flight then tracked north before turning east towards the Biarra Range and into a valley before descending to about 300 ft AGL. Shortly after, the aircraft completed a 180° turn, climbed to 3,900 ft and tracked towards Dalby Airport. At 0901, the aircraft landed at Dalby and was refuelled with about 263 L of fuel.

Figure 1: Flight to Dalby Airport

Figure 1: Flight to Dalby Airport

Source: Google Earth and OzRunways, annotated by ATSB

Recorded data showed the aircraft depart Dalby 11 minutes later, at about 0912, and tracked south‑east, climbing to a cruise altitude of about 2,500 ft (1,300 ft AGL). At 0927, the flight progressed over rising terrain and 3 minutes later was operating at about 400 ft AGL (Figure 2). At 0935, the aircraft turned left towards Main Range before completing a 180° turn between 300‑500 ft AGL. It then tracked south-east, climbing to about 1,000 ft AGL.

At about 0946, the aircraft passed over a mountain ridge at a height of about 200 ft AGL before turning left over another ridge at a height of about 270 ft AGL (2,900 ft AMSL). The aircraft then tracked north‑east, descending down a valley for 8 minutes at an altitude of about 1,200 ft (700 ft AGL).

Figure 2: Accident flight

Figure 2: Accident flight

Source: Google Earth and OzRunways, annotated by ATSB

At about 0955, the aircraft passed to the east of Gatton Airpark and turned right towards Lowood. Eight minutes later, the aircraft passed overhead Lowood and descended to 500 ft AGL before turning east towards Fernvale and the D’Aguilar Range. The flight data showed that at 1005, the aircraft passed over a hill at a height of about 200 ft AGL, before climbing to 700 ft AGL.

The flight progressed down a valley before completing another 180° turn while climbing to 1,000 ft AGL. After the turn, the aircraft descended to 800 ft (600 ft AGL) before turning right, back towards the D’Aguilar Range (Figure 3). During this turn, at 1007, the aircraft impacted terrain at an elevation of about 650 ft AMSL. The aircraft was destroyed, and all occupants were fatally injured.

Figure 3: Flight track and accident site

Figure 3: Flight track and accident site

Source: Google Earth and OzRunways, annotated by ATSB

Search and Rescue

About 30 minutes after departing the private property, the pilot had left a verbal flight note[3] with a person not associated with the operator to expect their arrival ‘late morning’. This person raised concern for the flight after several attempts to contact the pilot were unsuccessful, and notified the operator at 1309 that the pilot was missing. The operator then attempted to contact the pilot and made several calls to other locations to see whether the aircraft had landed at a different location.

At 1331, the operator notified Lowood police and at 1342, arranged for a helicopter from another Archerfield based operator to search for the missing aircraft. At 1344, the operator notified Airservices Australia who coordinated a search and rescue effort with the Joint Rescue Coordination Centre.

At about 1427, the helicopter departed Archerfield and located the wreckage shortly after. The helicopter pilot landed near the wreckage and proceeded to the site on foot, and then reported back to the operator that all of the aircraft’s occupants were deceased. Shortly after, a search and rescue helicopter arrived at the site and paramedics confirmed the fatalities.

Context

Pilot information

The pilot held commercial pilot licences (aeroplane and helicopter), with their last aeroplane flight review being conducted in March 2021 and operational proficiency check last completed in March 2022. The pilot also held an aeroplane instrument rating, but this was not current as the last renewal[4] was completed in October 2002 (valid until October 2003).

The pilot held a night VFR rating (helicopter), but this was also not current as the last proficiency check was completed in May 2019 (valid until May 2021). The pilot held a Class 1 aviation medical certificate, valid until October 2022.

Prior to the accident flight, the pilot had accumulated approximately 13,900 hours of aeronautical experience in helicopters and aeroplanes, of which about 475 hours were in command of the Cessna R182. The pilot also had about 96 hours of instrument flying experience and 22 hours of night VFR experience.

Aircraft information

The Cessna R182 Skylane RG is a 4-seat, high-wing, single‑engine aircraft with retractable landing gear. The accident aircraft was manufactured in the United States in 1978 and first registered in Australia in 1989 as VH-HZU before being purchased by Executive Helicopters in January 2020 and registered as VH-EHM. The aircraft was fitted with a Lycoming O-540 piston engine driving a 3 blade Hartzell constant speed propeller and was equipped for flight under both VFR and instrument flight rules (IFR).[5]

The last periodic maintenance inspection (100-hourly) was completed on 15 July 2022. Since then, the aircraft had accrued about 30 hours of flight time and had about 5,858 hours total time in service.

Terrain

The flight’s track towards Archerfield took the aircraft across the Great Dividing Range to the west of Brisbane with terrain elevations generally between 1,500‑2,000 ft AMSL. This area also contained numerous peaks between 2,000-2,700 ft (Figure 4).

Figure 4: Visual navigation chart extract showing terrain along the flight path

Figure 4: Visual navigation chart extract showing terrain along the flight path

Source: Airservices Australia and OzRunways, modified and annotated by ATSB

Meteorological information

Forecast

The graphical area forecast for the accident region forecast the following cloud conditions at the time of the accident (all heights AMSL):

  • broken[6] stratocumulus between 1,500-2,500 ft
  • broken cumulus/stratocumulus between 3,000-7,000 ft

Isolated smoke was forecast below 6,000 ft where the visibility reduced to 6,000 m. Isolated showers were forecast with 3,000 m visibility and the following cloud conditions:

  • broken stratocumulus between 1,000-2,500 ft
  • broken cumulus between 2,500-8,000 ft

The grid point wind and temperature chart for the region forecast 1,000 ft easterly winds between 9-13 kt, with temperatures 12-14 °C.

Airservices Australia held three National Aeronautical Information Processing System (NAIPS)[7] login records for the pilot in the 24-hour period before the accident. These were recorded at 0708, 0709 and 0925 on 29 August 2022.

Observations

The following METAR[8] observations from nearby airports were reported at 1000 (about 7 minutes before the accident):

  • Royal Australian Air Force Base Amberley (24 km south of accident site) – visibility 8,000 m, cloud scattered at 1,400 ft and broken at 2,800 ft[9]
  • Archerfield Airport (36 km south-east of accident site) – visibility at least 10 km, cloud scattered at 1,900 ft and 2,300 ft, and overcast at 3,300 ft

Several witnesses along the aircraft’s route from Dalby to Fernvale recalled seeing the aircraft flying at low altitude below cloud. One witness in Fernvale reported the aircraft flying at low altitude while heading east towards the D’Aguilar Range with the wings level and undercarriage retracted, before banking left (Figure 3) and disappearing from view as it was obscured by cloud. The witness also reported heavy low cloud, very light rain, and fog covering the Fernvale and surrounding area at the time.

Airspace

The Amberley military control zone extends from ground level up to an altitude of 8,500 ft (Figure 5). The airspace was active from 0800 to 2300 on 29 August and required a clearance to transit. Preliminary information indicated no record of a transit clearance request by the pilot, however, additional information is being collected by the ATSB to verify this.

Figure 5: Amberley control area

Figure 5: Amberley control area

Source: Airservices, annotated by ATSB

Site and wreckage information

The accident site was located within the D’Aguilar Range on a steep section of mountainous terrain covered with trees (Figure 6).

Figure 6: Accident site

Figure 6: Accident site

Source: ATSB

On-site evidence indicated that the aircraft was in a right turn with an angle of bank of about 47° when it collided with several trees, before impacting terrain about 28 ft vertically below the top of a ridge. The wreckage trail extended about 40 m from the initial impact point to the top of a ridge where most of the wreckage was located, including the engine. The propeller was located about 10 m forward of the main impact point.

On-site examination indicated that the engine was providing power at impact, with the landing gear and flaps in the retracted position. There was no evidence of an in-flight break-up or a pre‑existing defect with the flight controls.

Recorded Data

The aircraft was not fitted with a flight data recorder or cockpit voice recorder, nor was it required to be. Recorded data was obtained from various sources:

  • GPS flight track data from OzRunways
  • ADS-B data[10]
  • CTAF communications
  • CCTV footage
  • radar data

The flight track data indicated that the aircraft’s ground speed after departing Dalby was generally between 120-140 kt, indicative of normal cruise speeds.

Further investigation

The ATSB has examined the accident site and wreckage, interviewed witnesses, collected meteorological data, pilot and flight records and obtained aircraft tracking data.

The investigation is continuing and will include further review and examination of:

  • pilot training, qualifications, experience, and medical information
  • aircraft maintenance and flight records
  • operator procedures, flight notification practices and management systems
  • witness accounts
  • meteorological data
  • recorded data (CCTV, flight tracking, communications).

Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

A final report will be released at the conclusion of the investigation.

Acknowledgements

The ATSB would like to acknowledge the significant assistance provided by the Queensland Police Service during the onsite investigation phase and initial evidence collection activities.

[1]     The flight was operated under Civil Aviation Safety Regulations Part 135 (Air transport operations - smaller aeroplanes).

[2]     Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to fly the aircraft while maintaining visual separation from terrain and other aircraft.

[3]     Details of the route and timing of a proposed flight provided by the pilot-in-command of an aircraft, other than a notification submitted to Airservices Australia, and which is required to be left with a person who could be expected to notify appropriate authorities if the flight becomes overdue.

[4]     Before the introduction of the Civil Aviation Safety Authority (CASA) Part 61 licencing regulations in 2014, under Civil Aviation Regulation 5, pilots maintained instrument currency by completing an instrument ‘renewal’. Under Part 61, pilots maintained this currency by completing an ‘instrument proficiency check’.

[5]     Instrument flight rules (IFR): a set of regulations that permit the pilot to operate an aircraft in instrument meteorological conditions (IMC), which have much lower weather minimums than visual flight rules (VFR). Procedures and training are significantly more complex as a pilot must demonstrate competency in IMC conditions while controlling the aircraft solely by reference to instruments. IFR-capable aircraft have greater equipment and maintenance requirements.

[6]     Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘few’ indicates that up to a quarter of the sky is covered, ‘scattered’ indicates that cloud is covering between a quarter and a half of the sky, ‘broken’ indicates that more than half to almost all the sky is covered, and ‘overcast’ indicates that all the sky is covered.

[7]     The National Aeronautical Information Processing System (NAIPS) is a computerised, aeronautical information system. It processes and stores meteorological and NOTAM information as well as enables the provision of briefing products and services to pilots.

[8]     METAR: a routine aerodrome weather report issued at routine times, hourly or half-hourly.

[9]     Cloud heights are reported as above aerodrome elevation. Amberley elevation – 91 ft. Archerfield elevation – 65 ft.

[10]    Automatic Dependent Surveillance – Broadcast - A means by which aircraft, aerodrome vehicles and other objects can automatically transmit and/or receive data such as identification, position and additional data, as appropriate, in a broadcast mode via a data link.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2022

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.


Occurrence summary

Investigation number AO-2022-041
Occurrence date 29/08/2022
Location 36 km north-west of Archerfield Airport
State Queensland
Report release date 21/12/2023
Report status Final
Investigation level Defined
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Cessna Aircraft Company
Model R182
Registration VH-EHM
Serial number R18200431
Aircraft operator EXECUTIVE HELICOPTERS PTY LTD
Sector Piston
Operation type Part 135 Air transport operations - smaller aeroplanes
Departure point Dalby Aerodrome, Queensland
Destination Archerfield Aerodrome, Queensland
Damage Destroyed

Fatality on locomotive of train 4MB9, near Cullerin, New South Wales, on 25 August 2022

Summary

An investigation has commenced into a fatality on board the lead locomotive of train no. 4MB9 near Cullerin, New South Wales (NSW), on 25 August 2022.

On the afternoon of 25 August 2022, two SCT locomotives were hauling a containerised freight train north of Yass, NSW, en route to Bromelton, Queensland. For reasons not yet determined, while the train was still moving the driver left the driving cabin. After an extended period the driver's assistant stopped the train and left the driving cabin to ascertain the driver's whereabouts.

Shortly afterwards, the driver's assistant found the driver unresponsive on the locomotive footplate, having sustained fatal injuries.

This investigation is being led by the NSW Office of Transport Safety Investigations (OTSI). OTSI conducts rail investigations in NSW on behalf of the ATSB under the Transport Safety Investigation Act 2003 (Cwlth). OTSI investigators have largely completed evidence collection and analysis, with the draft report now commenced.

An interim report, which details factual information established during the course of the investigation, was released on 18 October 2023 (see below).

The final report will be released at the conclusion of the investigation. However, should a critical safety issue be identified during the course of the investigation, OTSI and the ATSB will immediately notify relevant parties, so that appropriate and timely safety action can be taken.

Last updated:

Interim report

Report release date: 18/10/2023

This interim report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Interim reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this interim report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.

This investigation is being conducted under the Transport Safety Investigation Act 2003 (Commonwealth) by the Office of Transport Safety Investigations (New South Wales) on behalf of the Australian Transport Safety Bureau in accordance with the Collaboration Agreement.

The occurrence

Victoria

On the morning of 25 August 2022, train no. 4MB9 from Altona, Vic. to Bromelton, Qld was prepared for traffic at SCT Logistics’ yard in Altona. The train consisted of locomotives SCT 013 and SCT 005, hauling 1,676 t consisting of 27 freight wagons. The first rostered crew for 4MB9 commenced duty at 0300 hours[1] and consisted of an SCT Logistics employed mentor driver and, an SCT Logistics driver who was learning the route from Altona to Wagga Wagga (521.160 km),[2] NSW.

Marshalled directly behind locomotive SCT 005 was a container wagon on which a single fuel tanker was placed. The fuel tanker was provided for the purpose of in-line fuelling[3] the locomotives enroute to the train’s destination of Bromelton, Qld. The mentor driver performed the task of connecting the fuel lines, multiple unit cable and main reservoir air supply between the locomotives and the fuel tanker. Once connected, the mentor driver tested the ‘fast pump’ and ‘gravity feed’ fuelling modes were operating between the fuel tanker and locomotives.[4]

After preparations were complete, 4MB9 departed Altona Yard about half an hour behind schedule at 0418. The delayed departure was due to track maintenance activities taking place on the Melbourne Metropolitan Network.

Four hours after departing Altona, 4MB9 arrived at Barnawartha, Vic. where a shunt was required to both detach and attach wagons before the train continued north (Figure 1).

Figure 1: Northeast line to Victoria / New South Wales border

Figure 1: Northeast line to Victoria / New South Wales border


Distances measured from Southern Cross station in Melbourne, Vic.
Source: ARTC, annotated by OTSI

While shunting at Barnawartha, the mentor driver elected to commence gravity feeding fuel from the in-line fuelling tanker to SCT 005. While the fuel usage by the locomotive had been minimal since departure from Altona, the mentor driver advised OTSI that they did this to assist the second rostered crew, who would be taking over the train at Wagga Wagga, NSW (521.160 km).

At 0859, 4MB9 departed Barnawartha, crossing the border into NSW shortly afterward.

New South Wales

At 0934, SCT Logistics’ LiveRun train coordinator contacted the driver’s assistant (second crew) who was to take over 4MB9 at Wagga Wagga. This crew, consisting of a driver and driver’s assistant, were employed by Momentum Rail to operate the SCT Logistics train. They were to take the train from Wagga Wagga to Leightonfield (Sydney), where they would change with a third crew, also employed by Momentum Rail. The train coordinator requested that the driver’s assistant (second crew) check that the in-line fuelling system was operating on 4MB9 and to report back. This gave SCT Logistics the opportunity to arrange manual fuelling of the locomotives by a road tanker on arrival at Leightonfield if required, in the event the in-line fuelling system was not working.

In interview, the mentor driver (first crew) told OTSI that as 4MB9 approached Wagga Wagga, they contacted the outbound driver’s assistant (second crew) by phone to advise that SCT 005 was in the process of being gravity fed fuel by the in-line fuelling system.

As a result, on arrival of 4MB9 at Wagga Wagga at 1052, the driver’s assistant (second crew) checked the fuelling status of SCT 005 and found the locomotive’s tank was full, with excess diesel fuel overflowing onto the track. The driver’s assistant switched off the valve between the fuel tanker and the locomotives, and isolated SCT 005 from the in-line fuelling system to stop the re-fuelling process. Prior to departure from Wagga Wagga, the driver’s assistant contacted the train coordinator to advise that gravity feed mode was working, with SCT 013 to be fuelled at a later stage. The train coordinator asked that the driver’s assistant verify that ‘fast pump’ mode was also operational when able to do so.

At 1101, on completion of the SCT Logistics / Momentum Rail crew changeover, 4MB9 departed Wagga Wagga for Leightonfield (23.700 km).

At 1256, the driver of 4MB9 stopped the train briefly at Harden (385.637 km) (Figure 2) to allow the driver’s assistant to setup the in-line fuelling system to fuel the front locomotive (SCT 013). In interview, the driver’s assistant told OTSI that at this time they opened the valve on the fuel tanker and depressed the in-line fuelling manual override button on SCT 013, to commence the gravity feed process.

Figure 2: NSW Main South Line – Goulburn to Wagga Wagga

Figure 2: NSW Main South Line – Goulburn to Wagga Wagga


Distances measured from Central station in Sydney, NSW.
Source: UGL Regional Linx, altered and annotated by OTSI

Although SCT 013 was fitted with a fuel sensor which relayed the volume of fuel in the locomotive fuel tank to the FIRE screen[5] on the driver’s console, the driver’s assistant advised this was inaccurate and not relied upon. As a result, at 1402 the driver stopped 4MB9 briefly at Yass Junction (318.011 km) (Figure 2) to allow the progress of the gravity fed fuelling to be checked. At this time, both the driver and driver’s assistant left the locomotive cabin to individually check the physical fuel gauges on each side of SCT 013’s fuel tank.[6]

After departure from Yass Junction, it is likely that the driver continued to monitor the fuel volume on SCT 013 via the electronic reading on the FIRE screen.

Accident sequence

As the train approached Gunning (278.566 km) (Figure 2), the driver swapped positions in the locomotive cabin with the driver’s assistant, allowing them to drive the train. As the driver’s assistant was soon to commence formal training[7] to progress to a driver’s role, this opportunity allowed them additional practical experience in operating a train.

At 1448, after departing Fish River (271.021 km), a lengthy uphill gradient commenced to the Cullerin Road overpass (258.845 km) (Figure 3). The driver instructed the driver’s assistant to select full traction power (8 notches) and to maintain that setting for the ascent of the grade.

Figure 3: Vicinity of the accident

Figure 3: Vicinity of the accident


The section of ascending track from Fish River to Cullerin Road overpass and final stopped location of 4MB9. The route of the railway line is depicted by a black line in the image.
Source: Google Earth, annotated by OTSI

As 4MB9 ascended the grade, the in-cab conversation between the driver and driver’s assistant turned to the progress of the in-line fuelling of SCT 013. Although the gravity feed had now been operating for about two hours, the 10,000 L capacity fuel tank on SCT 013 was only reading a fuel volume of about 5,600 L.

In interview, the driver’s assistant told OTSI that the driver of 4MB9 (who was now seated in the driver’s assistant seat) advised that they would temporarily leave the locomotive cabin to check the in-line fuelling circuit breakers in the vestibule. At 1459:36, while travelling at 61 km/h, 4MB9 passed under the Cullerin Road overpass and it was at this location that the driver’s assistant recalled the driver leaving the cabin and entering the vestibule. 

From the Cullerin Road overpass to Old Sydney Road level crossing (256.489 km), the gradient changed from uphill to a dip, requiring the driver’s assistant to temporarily reduce the traction power setting.

At 1501:22, 4MB9 now travelling at 74 km/h, passed over the Old Sydney Road level crossing, from which point the gradient changed to a predominantly downhill grade for the next 4 km. The driver’s assistant reduced the locomotive’s traction power to idle at this time. As the driver’s assistant required instruction on operating the train through this area, they left the cabin to find the driver who had not yet returned. When the driver’s assistant could not locate the driver in the vestibule, they opened the external door to check the right-hand side exterior of the locomotive and then the left-hand side exterior. It was while checking the left-hand side exterior that the driver’s assistant located the driver incapacitated, lying across the top handrail and up against the locomotive traction motor blower shroud (Figure 4). The driver’s assistant moved the driver from the handrail and laid them down onto the footplate, at which point they identified the driver had received a fatal head injury.

Figure 4: Location of driver (example locomotive)

Figure 4: Location of driver (example locomotive)

Note: the image is of an example locomotive, not the actual locomotive involved in the accident.
Source: NSW Police, annotated by OTSI

The driver’s assistant immediately returned to the locomotive cabin and shortly afterward applied full dynamic braking.[8] At 1503:09, with 4MB9 now travelling at 88 km/h, the driver’s assistant applied a ‘full service’[9] brake application.

At about 1504, the driver’s assistant made an emergency brake application and placed an emergency radio call to the network control centre. They advised the network control officer that 4MB9 had been involved in an accident and that the driver had been fatally injured. The driver’s assistant further advised the network control centre that the driver had been on the outside of the locomotive checking a ‘fuel switch’.

At 1504:28, 4MB9 came to a stop at 253.096 km. Emergency services arrived on scene at 1527.

Post-accident track inspections

Several hi-rail vehicle track inspections were undertaken during the week following the accident to check for lineside obstructions. These were:

  • 25 August 2022 (day of the accident): the preceding 15 km over which 4MB9 had travelled.
  • 26 August 2022: the preceding 35 km over which 4MB9 had travelled.
  • 1 September 2022: the preceding 100 km over which 4MB9 had travelled.

During these inspections, no object was identified as the cause of the driver’s fatal injury.


Context

Network

The section of track from Gunning to Cullerin was managed by the Australian Rail Track Corporation. Network control services were provided by its control centre at Junee, NSW.

Train crew information

The driver commenced with the Public Transport Commission (railways) in 1973, later qualifying as a train driver. After working for several rolling stock operators, the driver joined Momentum Rail in December 2017. The driver was assessed as medically fit four months prior to the accident.

The driver’s assistant worked as a truck driver for 7 years before joining the rail industry. They qualified as a driver’s assistant in December 2020. After working as a labour hire employee for another rolling stock operator, the driver’s assistant joined Momentum Rail in September 2021. The driver’s assistant was assessed as medically fit in November 2020.

In-line fuelling

General

In-line fuelling (ILF) was a method of fuelling locomotives enroute without stopping the train. Its purpose was to reduce dwell times, reduce staff interaction with fuelling equipment and realise cost-savings through the bulk-buying of fuel from a single source.

SCT Logistics operated ILF on the east-west corridor between Adelaide (Penfield), SA and Perth (Forrestfield), WA and, on the north-south corridor between Melbourne (Altona), Vic. and Bromelton, Qld. ILF required the placement of a fuel tanker on a flat container wagon immediately behind the locomotives (Figure 5).

Figure 5: ILF fuel tanker placement

Figure 5: ILF fuel tanker placement

Source: SCT Logistics, annotated by OTSI

Connections between the locomotives and fuel tanker to facilitate ILF were:

  • fuel pipe from the tanker to the locomotives to supply diesel fuel
  • main reservoir air pressure[10] from the locomotives to the tanker, to run the tanker’s fuel pump and test for fuel line leakages
  • multiple unit cable from the locomotives to the tanker for the supply of electrical power.

There were three modes of operation for ILF, which were:

  • Automatic mode: setup prior to depot departure, this mode required no further intervention from the train crew. Probes within the locomotive fuel tank would identify if the fuel level was low, at which point the ILF system would automatically commence refuelling the locomotives. Diesel fuel was delivered from the ILF fuel tanker to the locomotive using 2-minute alternating periods between gravity fed fuel (50–60 L/min) and air operated pump, pressurised fuel delivery (180 L/min). Once the probes within the locomotive fuel tank determined the fuel tanks were full, fuel delivery from the ILF fuel tanker was automatically stopped.
  • Fast pump mode: used when automatic mode was not working as a quick means to fuel the locomotive/s manually. In this mode, the train crew were required to depress an override button on the locomotive (to open the locomotive’s actuator valve), operate a valve override switch on the ILF fuel tanker and lastly, turn and hold a spring-loaded switch on the ILF fuel tanker. These actions allowed the delivery of air operated pump, pressurised diesel fuel (180 L/min). In this mode the locomotive in-tank fuel level probes were not functional. As such, the volume of fuel in the locomotive fuel tank was required to be monitored as fuel would overflow if the tank was overfilled.
  • Gravity feed mode: in the event both automatic and fast pump modes were unavailable, fuel could be gravity fed to the locomotives. In this mode, the train crew were required to depress an override button on the locomotive (to open the locomotive’s actuator valve) and operate a valve override switch on the ILF fuel tanker. These actions delivered gravity fed fuel (50–60 L/min). In this mode the locomotive in-tank fuel level probes were not functional. As such, the volume of fuel in the locomotive fuel tank was required to be monitored as fuel would overflow if the tank was overfilled.
Inspection observations

At the time of the accident, the driver’s assistant advised the network control centre that the driver had been outside on the locomotive’s footplate checking a ‘fuel switch’. It was observed that the location where the driver’s assistant found the driver in an incapacitated state was directly above:

  • two ILF cut off valves, which isolated either the locomotive’s fuel tank from the ILF fuel line or, isolated the ILF fuel line from the front locomotive headstock[11]
  • the locomotive’s actuator valve (Figure 6).

Figure 6: Location of the driver in relation to ILF equipment (example locomotive)

Figure 6: Location of the driver in relation to ILF equipment (example locomotive)

Note: the image is of an example locomotive, not the actual locomotive involved in the accident. In this example image, the locomotive’s ILF cut off valves (dotted box) and actuator (inset image) are depicted in the ‘closed’ position however, these were verified to be ‘open’, consistent with gravity feed mode, on the day of the accident.
Source: NSW Police, annotated by OTSI

After the accident, OTSI investigators attended SCT Logistics’ depot at Altona, Vic. to inspect an exemplar SCT class locomotive and the ILF system. During this inspection, it was found that when standing on the locomotive’s external footplate it was not possible to observe the position of the locomotive’s ILF cut off valves. However, it was found that by leaning hard up against the top handrail and leaning out past the locomotive’s profile, it was possible to observe the indicator located on the top of the locomotive’s actuator.
 

Safety action

SCT Logistics has taken the following proactive safety action since the accident:

  • issued an updated instruction regarding in-line fuelling operational modes and procedures, including restrictions for their use
  • issued an updated procedure prohibiting the exit of the locomotive cabin onto the external footplate or, being located outside the profile of the locomotive while it is in motion
  • the placement of warning stickers on doors leading from the locomotive vestibule onto the external footplate.

Further investigation

To date, the ATSB has:

  • gathered and undertaken analysis of locomotive event recordings and, network control and LiveRun voice recordings
  • inspected the rail corridor and gathered recorded vision of the corridor immediately prior to the accident
  • gathered information regarding the in-line fuelling system including its operation, operational modes and procedures
  • gathered information regarding accessing the external locomotive footplate during transit, including procedures and training materials
  • conducted several interviews with operational staff
  • gathered and undertaken analysis of reported lineside obstructions and remedial actions
  • reviewed evidence collected at the accident site and during post-accident track inspections.

The investigation is continuing and will include:

  • further review of permanent lineside obstructions and proximity to the train’s kinematic envelope
  • further review of vegetation management which encroaches the rail corridor
  • further review and examination of the reliability of the in-line fuelling system and, rolling stock operator monitoring of modes of operation
  • enterprise training for the in-line fuelling system
  • consideration of SCT Logistics and Momentum Rail contractual requirements, oversight and shared risk management.

Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.

A final report will be released at the conclusion of the investigation.

Rail safety investigations in New South Wales 

Most transport safety investigations into rail accidents and incidents in New South Wales (NSW) are conducted in accordance with the Collaboration Agreement for Rail Safety Investigations and Other Matters between the Commonwealth Government of Australia and the State Government of NSW. Under the Collaboration Agreement, rail safety investigations are conducted and resourced in NSW by the Office of Transport Safety Investigations (OTSI), on behalf of the ATSB, under the provisions of the Transport Safety Investigation Act 2003. 

The Office of Transport Safety Investigations (OTSI) is an independent statutory body which contributes to improvements in the safety of bus, ferry and rail passenger and rail freight services in NSW by investigating safety incidents and accidents, identifying system-wide safety issues and sharing lessons with transport operators, regulators and other key stakeholders. Visit www.otsi.nsw.gov.au for more information.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2023

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     All time references in this report are in local time (Eastern Standard Time).

[2]     All track distances are measured from Central station in Sydney, NSW, unless otherwise stated.

[3]     See In-line fuelling for further information.

[4]     The three operating modes were ‘automatic’, ‘fast pump’ and ‘gravity feed.’ See In-line fuelling for further information.

[5]     FIRE screen: a digital display screen on the driver’s console which provided information to the driver, e.g. speed, air pressures, tractive effort and fuel volume.

[6]     To ensure an accurate fuel reading, both physical gauges are checked and the two volume readings averaged to provide an accurate fuel reading. This allows for any locomotive sidewards tilt impacting the fuel volume readings due to track geometry.

[7]     This training was scheduled to be an ‘engine and air’ school, i.e. knowledge of locomotives, equipment and the airbrake system.

[8]     Dynamic braking is an electrical brake which creates a retarding force by changing the electrical fields in the locomotive’s traction motors from a traction to generator configuration.

[9]     Full service is the maximum braking capacity that can be achieved with the train’s airbrake system. Selected by the driver, it applies maximum braking capacity to all trailing wagons on the train.

[10]    Main reservoir air was produced by the locomotives’ air compressors. It was used for several of the train’s functions, including the braking system, horn and sanding equipment.

[11]    The headstock is at both the front and rear of the locomotive, below footplate level. It is the interface point for air, fuel and electrical connections between the locomotive and other coupled rolling stock.

Occurrence summary

Investigation number RO-2022-011
Occurrence date 25/08/2022
Location Near Cullerin
State New South Wales
Report release date 18/10/2023
Report status Interim
Anticipated completion Q1 2027
Investigation level Systemic
Investigation type Occurrence Investigation
Investigation phase Final report: Drafting
Investigation status Active
Mode of transport Rail
Rail occurrence category Lineside object strike
Occurrence class Accident
Highest injury level Fatal

Train details

Train operator SCT Logistics
Train number 4MB9
Track operator Australian Rail Track Corporation (ARTC)
Type of operation Freight
Consist 2 x SCT class locomotives, 26 x freight wagons (box, container, van)
Departure point SCT Altona depot, Victoria
Destination SCT Bromelton depot, Queensland
Injuries Crew – 1 fatal
Train damage Nil

Flight below minimum altitude involving Beech Aircraft Corp 95-B55, VH-ALR, 20 km north-north-east of Parafield Airport, South Australia, on 12 August 2022

Final report

Report release date: 15/05/2024

Executive summary

What happened

On 12 August 2022, a Beech Aircraft Corp 95-B55, registered VH‑ALR and operated by Hartwig Air, was being repositioned to Parafield Airport, South Australia after completing a series of non‑scheduled air transport passenger flights in the north of the state.

Weather conditions at Parafield when the aircraft arrived required the pilot to conduct an instrument approach procedure. During that approach, about 20 km north-north-east of Parafield and while flying in cloud, the pilot descended the aircraft below a segment minimum safe altitude, activating an automated minimum safe altitude warning to air traffic control.

An air traffic controller established communication with the pilot and advised them of their descent below the segment minimum safe altitude and issued a safety alert. The pilot immediately climbed the aircraft above the segment minimum safe altitude, then continued the approach and landed without further incident.

What the ATSB found

The ATSB found that the pilot was experiencing increased workload during the approach in cloud and turbulent conditions and did not detect their inadvertent descent below the segment minimum safe altitude, until they received the warning from the air traffic controller.

The activation of the air traffic control minimum safe altitude warning instigated communication checks with the pilot, which resulted in them being alerted to the aircraft’s descent below the segment minimum safe altitude and an immediate climb was commenced.

While conducting the approach, the pilot reported that they had been referring to a hand-held paper copy of the instrument approach procedure chart, as the aircraft’s control yoke did not have a chart holder, nor did the pilot have a document holder or kneeboard available, which increased the difficulty monitoring the check altitudes and segment minimum safe altitudes.

The aircraft was about 850 ft above the recommended profile with 7 NM to run when the pilot decided to continue the approach. Continuing the approach from that position required a higher‑than-normal descent rate and had potential to increase the pilot’s workload.

What has been done as a result

Following this incident, the operator arranged for an experienced instrument flight examiner to conduct additional training with the pilot in a synthetic training device.

Safety message

Conducting an instrument approach in instrument meteorological conditions is a high workload procedure, requiring close monitoring by the flight crew of the aircraft’s vertical and lateral navigation to assure it remains clear of terrain.

An important part of conducting the instrument approach required the continuous monitoring of the aircraft’s altitude relevant to the various segment minimum safe altitudes and having the instrument approach procedure chart available in a suitable location that minimises additional workload.

Pilots also need to remain vigilant about the relationship between the procedure commencement altitude and the constant descent final approach path, including that the correct waypoint has been identified for managing the descent profile and ensuring the distance-based check altitudes are correctly interpreted.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 12 August 2022, a Beech Aircraft Corp 95-B55, registered VH-ALR and operated by Hartwig Air, was being repositioned to Parafield Airport, South Australia after completing a series of non‑scheduled air transport passenger flights in the north of the state. Those flights had been conducted over two days and were operated under the instrument flight rules (IFR).[1]

The flights conducted on the day of the incident commenced in Innamincka and after refuelling the aircraft at Leigh Creek, the pilot had disembarked their passengers at Port Augusta. Weather conditions for those flights were influenced by a slow-moving low-pressure system to the south of Adelaide, resulting in a south-westerly onshore flow with low cloud, showers, reduced visibility and areas of moderate and severe turbulence. The pilot conducted area navigation (RNAV) global satellite system (GNSS) instrument approaches at Leigh Creek and Port Augusta.

The aircraft departed Port Augusta just after midday (local time) and was climbed to 5,000 ft above mean sea level for the flight to Parafield. As the aircraft approached Adelaide, the weather conditions in the Parafield control zone were unsuitable for a visual arrival and the approach controller instructed the pilot to track the aircraft to waypoint PPFNA,[2] one of the initial approach fixes (IAF) for the Parafield RNAV GNSS RWY 21R[3] instrument approach procedure.[4] The instrument approach procedure chart overlaid with the aircraft’s ground track is depicted at   Figure 1.

Figure 1: Parafield RNAV GNSS RWY 21R instrument approach procedure chart with VH‑ALR track overlaid

Figure 1: Parafield RNAV GNSS RWY 21R instrument approach procedure chart with VH‑ALR track overlaid

This image depicts the Parafield RNAV GNSS RWY 21R instrument approach procedure chart, overlaid with the aircraft’s ground track.

Source: Airservices Australia (ASA), modified by ATSB

The aircraft was 7 NM west of the IAF, when the approach controller cleared the pilot to descend from 5,000 ft to 4,000 ft, which was the instrument approach procedure’s minimum commencement altitude. The aircraft was approaching the IAF at an altitude of 4,000 ft when the controller issued the pilot clearance to commence the approach and to contact Parafield tower at the intermediate fix (IF), PPFNI.[5], [6]

Weather conditions for the approach were reported as turbulent, affecting the aircraft’s speed and attitude control, with the aircraft passing in and out of cloud. The pilot recalled that due to the conditions and to assist with speed control during the initial stages of the descent and approach, they had extended the landing gear and selected approach flap prior to the IAF.

After passing the IAF, the pilot turned the aircraft to track to the IF and commenced descent from 4,000 ft. The segment minimum safe altitude between the IAF and IF was 3,000 ft. During the first part of that segment, the pilot descended the aircraft at an appropriate rate. The aircraft was about 2 NM from the IF when it reached and then descended below the segment minimum safe altitude.

As the aircraft approached and then passed the IF, the descent rate increased slightly, with the pilot turning the aircraft to intercept the final approach track (Figure 1) at an altitude of about 2,000 ft. After the IF, the segment minimum safe altitude reduced to 2,200 ft.

Soon after the aircraft had passed the IF, the approach controller received an automated minimum safe altitude warning (MSAW) from the air traffic control (ATC) software-based monitoring system and attempted to establish radio contact with the pilot. The approach controller then used their ‘hotline’ intercom to contact the Parafield tower controller to check if the pilot had transferred to their frequency. The tower controller established communication with the pilot, advised them that they had descended below the minimum RNAV GNSS segment altitude and requested they confirm their flight conditions. The pilot reported that they were still in cloud. The tower controller then issued a safety alert and suggested an immediate climb. The pilot was already responding to the controller’s previous transmission and had entered a climb to establish the aircraft above the segment minimum safe altitude (Figure 2). In subsequent communication with the tower controller, the pilot elected to continue the approach.

The aircraft’s lateral track was within the required lateral tracking tolerances passing the final approach fix (FAF) PPFNF and about 300 ft above the recommended approach profile. The aircraft was about 4 NM from the runway at an altitude of 1,900 ft when the pilot reported to the tower controller that they were ‘visual’ and the final part of the approach was flown at an airspeed of about 100–110 kt.

The aircraft descent profile during the approach and the lateral tracking accuracy with reference to the global positioning system (GPS) course deviation indicator’s full-scale deflection is depicted in Figure 2.

Figure 2: Descent profile and lateral tracking accuracy during instrument approach

Figure 2: Descent profile and lateral tracking accuracy during instrument approach

The top graph depicts the descent profile of VH-ALR relative to the segment minimum safe altitudes during the instrument approach procedure. The grey dotted line is altitude derived from ADS-B data broadcast by the aircraft (25 ft increments), the purple line is the aircraft’s Mode C transponder altitude (100 ft increments). The lower image displays the lateral tracking accuracy of the aircraft during the instrument approach, together with the position of the full-scale deflection indicated on the course deviation indicator and the display of the GNS 430W.

Source: ATSB illustration of relevant data from the instrument approach procedure, Airservices Australia and FlightRadar24.

Context

Pilot information

The pilot held a Commercial Pilot Licence (Aeroplane) with an instrument rating and multi-engine endorsement.[7] The pilot was required to use vision correction when exercising their licence privileges. At the time of the incident, they had accrued a total aeronautical experience of approximately 1,200 hours, including 90 hours on multi-engine aircraft, 50 hours of which were on Baron series[8] aircraft. Most of the pilot’s Baron flying had been conducted under the instrument flight rules (IFR). Included in their aeronautical experience was about 60 hours of instrument flight time.

The pilot had completed an instrument proficiency check within the previous 12-month period and had recently completed a practice RNAV approach in VH-ALR at Ceduna. Prior to departing on the series of flights associated with the charter, the pilot had also conducted practice instrument landing system and RNAV approaches for Adelaide Airport, using a Civil Aviation Safety Authority (CASA)-approved synthetic training device.

The pilot recalled that they were well rested prior to commencing duty on the morning of the incident. Upon arriving at Parafield Airport, they had been on duty for more than 5 hours and had flown about 4 hours, including sectors in turbulent conditions and with relatively high workload. For the instrument approach into Parafield, the pilot reported feeling ‘moderately’ tired.[9]

Aircraft information

The aircraft was equipped with a conventional set of analogue flight instruments. It was also fitted with a 2-axis autopilot, capable of providing control guidance in the pitch and roll axes. During their post-incident interview, the pilot recalled the autopilot functionality was useful during cruise, but they wouldn’t normally use it when conducting instrument approaches.

VH-ALR was equipped with two, 3-pointer pressure-sensitive altimeters, including one directly in front of the pilot. The altimeters responded to pressure variations in the atmosphere and indicated the aircraft’s altitude above the selected pressure datum, by the pilot reading the relationship between the three indicating pointers.[10] These types of 3‑pointer altimeters are common in general aviation aircraft. Research has shown that such altimeters can be associated with misreading errors, including misreading the altitude by 1,000 ft.[11]

The aircraft was equipped with an assigned altitude indicator, which was designed to be used as a reminder of the altitude assigned by air traffic control (ATC). Altitudes could be manually set by means of individual thumb wheels, but no aural or visual alerts were provided when reaching or leaving the set altitude. The aircraft did not have an altitude alerting system, nor was it required for the type of aircraft and operation.[12]

For conducting RNAV (GNSS) instrument approaches, the aircraft had two global positioning system (GPS) receivers, a Garmin GNS 430W and a Garmin GTN 750. The display panels for the GPS receivers were located to the right of the engine control quadrant. The GTN 750 comprised a moving map display with touch screen functionality and the GNS 430W included the unit’s operating controls and a smaller display panel. The GNS 430W was installed directly below the GTN 750. The selected instrument approach procedure would crossfill between the two units. Neither the GNS 430W or the GTN 750 units could provide vertical profile guidance during the approach.

Meteorological information

The pilot obtained the relevant metrological forecasts prior to departing Innamincka on the morning of the incident. The weather conditions encountered during the flights were consistent with the forecast.

Affecting the aircraft between Port Augusta and Parafield at the selected cruise altitude was broken[13] cumulus and stratocumulus cloud and south westerly winds of about 25 kt. Scattered showers of rain with reduced surface visibility (4,000 m)[14] were forecast with towering cumulus cloud and isolated[15] light to moderate thunderstorms with rain and reduced surface visibility (2,000 m) with cumulonimbus cloud. Moderate turbulence[16] was forecast in cumulus/stratocumulus cloud and severe turbulence[17] and icing in towering cumulus/cumulonimbus cloud and thunderstorms. The freezing level was forecast to be 5,500 ft.

The Parafield Airport forecast (TAF) current at the time VH-ALR departed Port Augusta indicated that an instrument approach would likely be required arriving Parafield, with light showers of rain and broken cloud, 1,600 ft above the aerodrome elevation. The Parafield aerodrome weather reports (METARs) were automatically generated every 30 minutes for routine reports, or as special reports (SPECI) at other times when one or more meteorological elements either deteriorated or improved around specified criteria. A SPECI report was issued 1300 (closest to the time of the aircraft’s arrival), indicating broken cloud 1,700 ft above the aerodrome and overcast cloud at 2,300 ft, but with surface visibility greater than 10 km. Those conditions indicated that a pilot conducting the RNAV GNSS RWY 21R approach and flying the recommended 3‑degree approach profile, could expect to become visual with the runway at about the final approach fix (FAF).

Instrument approach

A RNAV GNSS was a two-dimensional (2D) instrument approach procedure flown using an onboard GPS receiver that complies with relevant airworthiness certification standards, to generate lateral/tracking guidance and the distance to run to next waypoint, allowing for safe navigation of an aircraft operating in instrument meteorological conditions to land at an aerodrome. If the pilot establishes the required visual reference with the runway during the approach, they continue the approach and land. If the required visual reference is not established, the pilot conducts the procedure for a missed approach.

The RNAV GNSS instrument approach procedure chart includes the approach course (comprising a series of waypoints) and information relevant to the vertical navigation of the aircraft. The descent profile was designed to provide a constant descent final approach (CDFA) path from the procedure altitude[18] to an altitude from which a straight-in landing or a circling procedure can be completed. Significantly, the position at which the CDFA intersected the procedure altitude varied between approaches, but occurred during the intermediate or final approach segments. The CDFA angle was shown on the chart’s profile diagram, together with a CDFA altitude/distance scale and advisory crossing altitudes. After commencement of the CDFA, the profile diagram and altitude/distance scale also included the crossing altitude for each of the waypoints.

Each segment of the RNAV GNSS instrument approach procedure specified one or more segment minimum safe altitudes, which were identified by shading on the chart’s profile diagram. When conducting a CDFA, pilots were expected to follow the descent profile, but monitor the descent to ensure the aircraft remains at or above the applicable segment minimum safe altitude.[19]

The instrument approach procedures were pre-programmed in the GPS database from which the pilot selected and activated the required approach. The aircraft’s position relative to the approach course was indicated on the display panels of the GPS receivers and also on the instrument panel’s course deviation indicator displays. The display panel of the GNS 430W receiver provided various operational information for the pilot’s management of the approach, including the current approach segment, the distance to run to the next waypoint and the aircraft’s groundspeed.

The GPS receivers were equipped with receiver autonomous integrity monitoring (RAIM).[20] The pilot recalled they had checked for predicted RAIM outages before arming the approach and there were none indicated. There were no RAIM messages displayed during the conduct of the instrument approach, indicating that the GPS calculated positions were within the required tolerance to conduct the approach.

Operational information

The ATC recordings indicated the pilot had correctly completed the read-back of the QNH[21] provided by the approach controller and the transponder indicated altitude from VH-ALR was consistent with the aircraft operating at the assigned altitude.

The pilot used the aircraft’s flight instruments and flight controls to steer the required approach course, make the required turns to intercept the next approach segment and manage the vertical profile of the descent.

The pilot indicated during interview that they had access to a portable electronic device with electronic flight bag (EFB) capability.[22] At the time of the incident, the operator did not hold a CASA approval to use EFBs, so the pilot also carried printed paper copies of the instrument approach procedure.[23] The aircraft’s control yoke did not have a chart holder, nor did the pilot have a document holder or kneeboard available. Consequently, the pilot reported that the paper chart was held in their hand when referring to it during the approach, including when checking altitudes, tracks and distances.

The pilot had anticipated that weather conditions at Parafield could necessitate an instrument approach and that they had reviewed the Parafield RNAV GNSS approach procedure at breakfast on the morning of the incident and again, prior to departing Port Augusta. The pilot recalled that they had identified the number of segment minimum safe altitude steps during their preflight reviews and briefing of the Parafield RNAV GNSS instrument approach procedure, particularly noting the close proximity of the final approach profile to several of those steps and planned to fly a constant profile descent during the approach. Prior to commencing the approach, they had identified that 3,000 ft was the segment minimum safe altitude prior to the intermediate fix (IF) and did not intend to descend the aircraft below that altitude. When conducting any descent, their normal procedure was to self-announce when there was 1,000 ft to run, but on this occasion the procedure was of limited use given that the descent commenced 1,000 ft above the intermediate level-out altitude.

Approaching the IF the pilot recalled concentrating on managing the aircraft’s speed in the turbulent conditions and monitoring the distance to commence the turn to intercept the final approach track. 

The pilot recalled that they had not yet reached the FAF when the tower controller advised them that they had descended below the minimum altitude, and immediately commenced a climb to above the segment minimum safe altitude. In those weather conditions, the pilot wanted to complete the approach and land as soon as practicable and when the controller asked their intentions, the pilot had elected to continue the approach.

The ATSB used the available data to estimate the aircraft’s airspeed during the final approach, which was within the required handling speeds for that approach segment.[24]

When reviewing the circumstances of the occurrence, the pilot felt those tasks had been prioritised to the detriment of their monitoring the aircraft’s altitude. The pilot did not believe that the descent below the segment minimum safe altitude was because they had misread the three‑pointer altimeter.

Since the occurrence, the pilot had considered that conducting the missed approach procedure was also an option, that could have helped manage any increased workload associated with continuing the approach and they had sufficient fuel to cover that contingency.

The pilot reviewed the Parafield RNAV GNSS RWY 21R instrument approach procedure after the occurrence and had compared that approach with the other procedures flown that day, they noted the variation between how the altitude/distance scales were presented and the waypoints that the altitudes and distances referred to.

The ATSB reviewed the instrument approach procedures flown by the pilot on the day of the incident and noted:

  • arriving at Leigh Creek, the procedure profile depicted a level segment from the IAF to the IF, and the CDFA path commenced about 4.5 NM prior to the FAF
  • arriving at Port Augusta, the procedure profile depicted the aircraft crossing the IAF at a constant altitude, but the CDFA path commenced about 1.9 NM prior to the IF
  • arriving at Parafield from the IAF waypoints PPFNA or PPFND, the procedure profile depicted an intermediate descent commencing at the IAF, but with a segment minimum safe altitude of 3,000 ft until after passing the IF (PPFNI) with the CDFA path commending 4.1 NM prior to the FAF.

For all approaches flown that day, the altitude/distance scale on the profile diagram provided information for the CDFA path, including the waypoint crossing altitudes. In the case of the Parafield approach, the waypoint PPFNI was also denoted as an IAF at an altitude of 3,000 ft.[25]

Safety analysis

On 12 August 2022, a Beech Aircraft Corp 95-B55, registered VH-ALR was being operated on an instrument approach procedure into Parafield Airport, South Australia. During that approach and while flying in cloud and turbulent conditions, the pilot descended the aircraft below a segment minimum safe altitude, activating an automated minimum safe altitude warning to air traffic control. Air traffic control contacted the pilot and advised the pilot of their descent below the segment minimum safe altitude and issued a safety alert. The pilot immediately climbed the aircraft above the segment minimum safe altitude, then continued the approach and landed without further incident.

The ATSB was satisfied that the pilot was adequately rested prior to commencing their duty period. Although the pilot reported that their fatigue levels had increased during the flight, that was to be expected given the weather conditions during the flights conducted that day.

The ATSB concluded there were no issues with the set up or functionality of the aircraft’s altimeters, meaning correct altitude information was available to the pilot. As such, the following analysis will consider factors associated with the descent below minimum safe altitude, use of a paper copy of the instrument approach procedure chart, the pilot’s response to the minimum safe altitude alert warning and the resulting steeper than normal approach to land.

The weather conditions in the vicinity of Parafield required the pilot to conduct an instrument approach. The aircraft was maintaining 4,000 ft above mean sea level as it approached the initial approach fix PPFNA and had been configured to commence the instrument approach procedure. The initial descent from 4,000 ft was conducted at a rate that achieved an approximate 3-degree descent profile.

The pilot had stated that they had left 4,000 ft at commencement of the approach with the intention of levelling out at 3,000 ft. The pilot’s recollection was that descent below the segment minimum safe altitude was not the result of misreading the altimeter or instrument approach procedure, but more due to being distracted by workload in the turbulent weather conditions. That included monitoring the distance to run to the intermediate fix, to initiate the turn to intercept the track for the final approach. Conducting an instrument approach in instrument meteorological conditions added to a high workload procedure, requiring close monitoring of the aircraft’s vertical and lateral navigation by the pilot.

The instrument approach procedure included five segment minimum safe altitudes and the constant descent final approach (CDFA) path that passed close to those limits, which necessitated close monitoring during the descent. During the instrument approach, the pilot would have used one hand on the control column to fly the aircraft, and the other hand to operate the engine and other ancillary controls. The pilot’s use of a paper copy of the instrument approach procedure chart without a chart holder or kneeboard available, made the task of referring to the chart information less convenient and potentially increased the likelihood of misinterpreting check altitudes for the descent or segment minimum safe altitudes that applied.

Following the incident, the pilot reviewed the Parafield instrument approach procedure, together with the other procedures they had flown that day and correctly identified that each procedure’s CDFA path commenced at different positions in relation the initial approach and intermediate fixes. However, they probably had not correlated the relationship between the procedure altitude for commencement of the CDFA path and the significance of that position with the commencement of altitude/distance scale on the instrument approach procedure’s profile diagram. This increased the potential for the pilot to misinterpret the altitude/distance scale and associate the published altitude with the distance to run to an incorrect or out of sequence waypoint.

Although the pilot was experiencing a high workload as the aircraft approached the intermediate fix, they had accurately intercepted the inbound track and had immediately initiated a climb of the aircraft when the tower controller advised their descent below the minimum procedure altitude. Although the aircraft had descended below the segment minimum safe altitude, the lateral tracking of the aircraft was accurate and remained within the lateral tracking requirements for the RNAV GNSS procedure.

The pilot climbed the aircraft above the 2,200 ft segment minimum safe altitude for that stage of the approach and continued the climb. That resulted in the aircraft being about 850 ft above the recommended profile with 7 NM to run to the missed approach point when the tower controller asked the pilot their intentions, and the pilot indicated they would continue the approach. Continuing the approach from that position did require a higher-than-normal descent rate and had potential to increase the pilot’s workload. However, the pilot managed the descent of the aircraft to progressively intercept the approach profile, the aircraft’s speed was maintained within the required parameters for the approach and the lateral tracking was within the required tolerances. The aircraft was about 400 ft above the recommended CDFA path at the final approach fix, with 5 NM to run to the missed approach point and soon after, the pilot reported to the tower controller that they were visual.

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the flight below minimum altitude involving Beech Aircraft Corp 95-B55, registration VH-ALR near Parafield Airport, South Australia on 12 August 2022.

Contributing factors

  • Approaching the intermediate fix while conducting a RNAV GNSS approach in instrument meteorological conditions and turbulence, the pilot’s workload increased and they did not identify the inadvertent descent below the segment minimum safe altitude.

Other factors that increased risk

  • The pilot reported that they were using a hand-held paper copy of the instrument approach procedure chart, which increased the difficulty monitoring the check altitudes and segment minimum safe altitudes for the various stages of the approach.
  • After climbing the aircraft above the segment minimum safe altitude, the pilot elected to continue the approach which necessitated a steeper than normal descent.

Other findings

  • The activation of the minimum safe altitude warning on the approach controller's console instigated communication checks with the pilot, which resulted in them being alerted to the aircraft’s descent below the segment minimum safe altitude and an immediate climb was commenced.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.

Safety action by Hartwig Air

Following this incident, the operator arranged for an experienced instrument flight instructor/examiner to conduct additional training with the pilot in a synthetic training device.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the pilot of VH-ALR
  • Airservices Australia
  • Bureau of Meterology.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the following directly involved parties:

  • the pilot of VH-ALR
  • Hartwig Air
  • Civil Aviation Safety Authority
  • Airservices Australia
  • Bureau of Meterology.

There were no submissions received.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through: 

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2024

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Instrument flight rules (IFR): a set of regulations that permit the pilot to operate an aircraft in instrument meteorological conditions (IMC), which have much lower weather minimums than visual flight rules (VFR). Procedures and training are significantly more complex as a pilot must demonstrate competency in IMC conditions while controlling the aircraft solely by reference to instruments, rather than by outside visual reference. Typically, this means flying in cloud or limited visibility. IFR-capable aircraft have greater equipment and maintenance requirements.

[2]     Waypoint: A defined position of latitude and longitude coordinates, primarily used for navigation. These waypoints were incorporated to the GPS receiver’s navigation database and could not be edited by the user. Regular updates were made to the navigation database and ensured the current/correct approach procedure was available.

[3]     Runway number: the number represents the magnetic direction of the runway centreline, and is expressed in 10 degree increments of azimuth. The runway identification may include L, R or C as required for left, right or centre.

[4]     An RNAV GNSS approach is a type of instrument approach procedure that uses a GPS receiver that complies with the relevant airworthiness certification standards, to provide lateral tracking information for the pilot to conduct the approach.

[5]     The relatively late approach clearance was due to visual flight rules (VFR) aircraft operating in the Parafield circuit area. An approach clearance could only be issued once all the VFR aircraft operating in the Parafield control zone were on the ground.

[6]     Waypoint PPFNI was the intermediate fix for the procedure when being conducted from offset sectors (PPFNA and PPFND). For a straight-in approach, PPFNI was designated as the IAF at an altitude of not below 3,000 ft.

[7]     This included 2D and 3D instrument approach operations in instrument meteorological conditions, which included RNAV GNSS procedures. The pilot’s instrument rating and multi-engine endorsement was issued in 2017. Since that time, they had completed 2 instrument proficiency checks.

[8]     The Baron series of aircraft includes the Beech Aircraft Corp 95-B55.

[9]     During interview, the pilot was asked to make a subjective assessment of their fatigue level at the time of the occurrence, using the Samn-Perelli seven-point fatigue scale. The pilot estimated that they had started their duty period fully alert, wide awake (scale point ‘1’), but at the time of the occurrence their fatigue levels had increased, and they were moderately tired (scale point ‘5’).

[10]    Hundreds of feet were indicated by a long and narrow pointer needle, thousands of feet by a short and wide pointer needle and tens of thousands of feet by a long/thin needle with a triangle symbol at the pointer’s tip.

[11]    A summary of research and guidance regarding the design of altimeters is included in Appendix A of the ATSB Aviation Occurrence Report AO-2020-017, Controlled flight into terrain involving Cessna 404, VH-OZO 6 km south-east of Lockhart River Airport, Queensland, on 11 March 2020. This report is available to download from the ATSB website (AO-2020-017).

[12]    An altitude alerting system provides an aural alert (tone) and/or a visual alert when an aircraft on climb/descent approaches the designated altitude and when deviating from that altitude during cruise. Aircraft conducting IFR operations in controlled airspace were required to have either an assigned altitude indicator or an altitude alerting system. For piston-engine aircraft, an altitude alerting system was only required for IFR operations at altitudes 15,000 ft above the standard atmospheric pressure datum 1013.25 hPa.

[13]    Broken describes cloud coverage between 5 to 7 eighths (oktas) of the sky (except for cumulonimbus and towering cumulus cloud).

[14]    Scattered describes well separated features that affect or are forecast to affect, an area with a maximum spatial coverage from 50% to 75%.

[15]    Isolated describes individual features that affect or are forecast to affect, an area with a maximum spatial coverage of up to 50%.

[16]    Moderate turbulence describes appreciable changes in attitude and/or altitude in rapid bumps or jolts, but with the pilot being able to control the aircraft.

[17]    Severe turbulence describes large abrupt changes in attitude and/or altitude, resulting in momentary loss of control of the aircraft flightpath.

[18]    The procedure altitude accommodates a stabilised descent at a prescribed descent gradient/angle in the intermediate/final approach segments.

[19]    Descent below the recommended CDFA to the segment minimum safe altitude can be conducted at pilot discretion but was not a recommended technique.

[20]    Availability of RAIM during the conduct of an RNAV GNSS approach provides an assurance of the integrity of the navigation system and that the calculated position is within the required tolerance for the procedure being flown.

[21]    QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean seal level.

[22]    An EFB can replace traditional paper products in an aircraft, store and display aviation data and perform calculations. This typically also includes functionality such as a moving map display with relevant information overlaid.

[23]    Holders of an air operator certificate required CASA approval before their crews could use an EFB. Operators were required to provide CASA with an exposition including information, procedures, and instructions for the use of EFBs.

[24]    The handling speed stipulated for a category B aircraft during the final approach segment was 85 to 130 kt.

[25]    This configuration for the approach allowed aircraft arriving from the north-east to commence the approach at waypoint PPFNI.

Occurrence summary

Investigation number AO-2022-039
Occurrence date 12/08/2022
Location Near Parafield Airport
State South Australia
Report release date 15/05/2024
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Flight below minimum altitude
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Beech Aircraft Corp
Model 95-B55
Registration VH-ALR
Serial number TC-1739
Aircraft operator Bruce Hartwig Flying School Pty Ltd
Sector Piston
Operation type Part 135 Air transport operations - smaller aeroplanes
Departure point Port Augusta Airport, South Australia
Destination Parafield Airport, South Australia
Damage Nil

Assistance to the Sports Aviation Federation of Australia in the examination of components from a fatal accident involving a weightshift microlight on 3 March 2021

Summary

On 3 March 2021, an AirBorne Edge XT-912 weight-shift microlight, registered T2-6160, broke up in flight and collided with terrain near Exmouth, Western Australia. Both occupants were fatally injured and the aircraft was destroyed. 

The Sports Aviation Federation of Australia (SAFA) requested technical assistance from the ATSB in the examination of some failed components from the aircraft. To facilitate this assistance, the ATSB initiated an external investigation under the provisions of the Transport Safety Investigation Act 2003.

The ATSB has concluded the examination of the components, and provided the results of that work to SAFA on 22 July 2022.

SAFA is responsible for and will administer the release of any information from the accident investigation. Any enquiries relating to the matter should be directed to SAFA at www.safa.asn.au

Occurrence summary

Investigation number AE-2021-012
Occurrence date 03/03/2021
Location near Exmouth
State Western Australia
Report release date 22/07/2022
Report status Final
Investigation type External Investigation
Investigation status Completed
Mode of transport Aviation
Highest injury level Fatal

Aircraft details

Model AirBorne Edge XT-912
Registration T2-6160
Sector Sport and recreational
Damage Destroyed

Fuel starvation event involving Cessna 310, VH-JQK, near Sunshine Coast Airport, Queensland, on 18 August 2022

Final report

Report release date: 05/05/2023

Executive summary

What happened

On 18 August 2022, a Cessna 310R, registered VH-JQK, was being operated by Aircraft Australia on a training flight from Redcliffe, Queensland.

After completing asymmetric training sequences to the east of Brisbane, the crew flew towards the Sunshine Coast Airport to conduct instrument training. While establishing a practice instrument approach, the engines started surging alternatively. The instructor declared a MAYDAY. On descent the crew switched from the auxiliary to the main fuel tanks, which rectified the engine issues, and then completed an uneventful landing.

What the ATSB found

The crew did not completely follow the operator’s pre-flight and in-flight fuel management procedures, which required pilots to:

  • cross-check fuel quantity prior to a flight with a visual confirmation or fuel log
  • monitor fuel levels and tank selection every 30 minutes during a flight.

Further, the instructor was unaware of the fuel system configuration of the Cessna 310R being operated, believing the aircraft was fitted with larger auxiliary tanks than was the case. The operator had inconsistent and incomplete documentation for the aircraft, and the fuel selector plaques contained contradictory information about the size of the auxiliary tanks.

What has been done as a result

Aircraft Australia implemented a new fuel log specific for the Cessna 310R. Additionally, an internal memo outlining the changes to the data sheet for the Cessna 310R was released to ensure all pilots and students are aware of the complex fuel configuration of the aircraft. Furthermore, the operator has requested replacement of the fuel selector plaques to ensure the correct data labels are installed.

Safety message

Accidents involving fuel mismanagement are an ongoing aviation safety concern and are a reminder of the importance of monitoring fuel levels prior to, and during, flight.

This occurrence reinforces the need to:

  • be fully familiar with the aircraft fuel system’s operation and capacity
  • conduct a thorough pre-flight inspection including the cross checking of fuel quantity and quality
  • determine the expected rate of fuel consumption prior to flight and monitoring fuel consumption during flight to confirm performance
  • ensure the appropriate tank selections are made
  • ensure all aircraft documentation and placarding is up to date and readily available.

Fuel management related accidents have been published by the ATSB in Avoidable Accidents No. 5 - Starved and exhausted: Fuel management aviation accidents (AR-2011-112) which outlines strategies and key messages for fuel management.

Methods for cross-checking fuel on board before flight are published by the Civil Aviation Safety Authority in Advisory Circular AC 91-15 Guidelines for aircraft fuel requirements.


The investigation

Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.

The occurrence

On 18 August 2022, a Cessna 310R, registered VH‑JQK and operated by Aircraft Australia, was being prepared at Redcliffe, Queensland, for a multi-engine training endorsement flight involving an instructor and a trainee instructor.

The trainee instructor dipped the fuel tanks and determined there was 309 litres of total fuel onboard. They were unable to recall the split of fuel between the main and auxiliary fuel tanks. Both crew recalled after the event that the fuel quantity was not cross-checked[1] between the dipsticks and fuel gauges.

The trainee instructor conducted a pre-flight briefing with the instructor outlining the asymmetric training sequences which would be conducted. The flight was expected to last 1.5–2 hours.

While taxiing, the instructor checked the fuel gauges and continued to the runway. The instructor recalled thinking at the time that both the main tanks and the auxiliary tanks were full. The flight departed Redcliffe at about 1423 and proceeded to the east over Moreton Island.

About 30 minutes into the flight, the trainee instructor switched from the main to the auxiliary fuel tanks and began the asymmetric training sequences. The trainee instructor was unable to recall why this was done. Neither pilot could later recall any fuel gauge readings during the flight.

At about 1459 the pilots decided to conduct an instrument approach to Sunshine Coast Airport to prepare the trainee instructor for an instrument rating training endorsement. The trainee instructor went under the hood[2] to simulate instrument meteorological conditions.[3]

At about 1515, the instructor made contact with the Sunshine Coast air traffic control tower controller and was cleared to fly to the west. Shortly after, the aircraft was cleared for an instrument approach and the crew began to fly the outbound leg of the approach .

At 1517 the instructor began pre-landing checks and the flaps[4] were extended to 15°. At about that time, both engines began to surge, and the instructor conducted the first 5 steps of the emergency checks including flap retraction and then unsuccessfully attempted to determine the affected engine (Figure 1). The trainee instructor noticed fuel streaking from the main tank vents, indicating fuel venting.[5] Shortly after, the engines began to operate normally for about 20 s before they started to surge alternatively with a corresponding reduction in power and yawing[6] of the aircraft.

Figure 1: Occurrence flight

Figure 1: Occurrence flight

Source: Google Maps annotated by the ATSB

At about 4,200 ft and tracking in an easterly direction, the instructor declared a MAYDAY on the tower frequency and requested direct track for runway 13.[7] The controller cleared the aircraft to descend to 1,500 ft and to track for runway 13.

After descending to 1,500 ft and when established on downwind for a visual approach to runway 13, the pilots began further troubleshooting. The instructor selected the fuel pumps on and identified that the fuel selectors were still set to the auxiliary tanks. After switching back to the main tanks, both engines regained power.

The aircraft landed and taxied to the general aviation parking area. The crew later reported that, after landing, the auxiliary tanks’ fuel gauges read zero. The auxiliary tanks were dipped and were confirmed to be empty. The main tanks were also dipped and found to be full. There were blue streaks indicating that there had been fuel venting overboard.

After discussion with maintenance staff, the pilots conducted a successful ground run of the aircraft on the main tanks and did not identify any problems. The pilots then flew back to Redcliffe without refuelling.
 

Context

Pilot information

Instructor

The instructor held a commercial pilot licence (aeroplane), issued in 2017 with class ratings for single and multi-engine aircraft. The instructor had a total of about 2,100 flying hours of which, about 212 hours was instructional flying. The instructor began the role of head of flying operations for the operator in May 2022 after about 15 months of non-flying. The instructor had totalled 21.1 hours on VH-JQK, the operator’s only Cessna 310, in the previous 5 months. Including previous flights in 2017–2020, the pilot had accrued an estimated about 500–600 hours on Cessna 310 variants.

Trainee instructor

The trainee instructor held a commercial pilot licence (aeroplane), issued in 2019 with class ratings for single- and multi-engine aircraft. They completed an instructor rating at the beginning of 2022 before commencing to instruct on single engine aircraft and to conduct aerial work operations. At the time of the occurrence, the trainee instructor had about 138 instructional hours and a total of about 470 flying hours of which 8 were on the Cessna 310R, all in VH-JQK.

Aircraft information

The Cessna 310R was a twin-engine, low-wing, 6-seat, unpressurised aircraft equipped with retractable landing gear. The aircraft was fitted with Continental IO-520-M piston engines. The aircraft was manufactured in 1978, and first registered in Australia on 31 October 1989. The operator became the registration holder on 9 June 2022.

Fuel tank configuration

VH-JQK’s fuel system consisted of main tanks at each wing tip and auxiliary tanks in each outboard wing section. The combined usable capacity of the main fuel tanks was about 100 US gallons (378 L), and 40 US gallons (151 L) for the auxiliary tanks. The aircraft was also fitted with a nacelle fuel tank which had been disconnected and was no longer used. The main aluminium tanks were vented to the atmosphere.

Cessna 310R aircraft could be configured with the main tanks only, or with additional auxiliary and/or wing locket tanks (see Pilot’s operating handbook). The auxiliary tanks came in two sizes, the smaller 40-gallon size and the large 60-gallon size.

The instructor had previously flown Cessna 310R aircraft with 60-gallon auxiliary tanks and assumed that VH-JQK was similarly equipped, not knowing that it had 40-gallon tanks.

Information on the aircraft fuel system for the Cessna 310R was provided by:

  • the aircraft fuel selector plaques
  • the fuel gauges in the aircraft
  • the pilot’s operating handbook
  • the company operations manual.
Fuel selector plaques

The aircraft had one fuel selector for each engine, on the floor between the pilot seats. This allowed for the selection of main fuel tanks, auxiliary fuel tanks, cross-feed and fuel shutoff through the wing selector valves located in each respective wing. The fuel selectors also had plaques defining the amount of fuel in each tank in US gallons.

The fuel selector plaques displayed the amount of fuel available in each of the tanks. Fuel selector plaques under the Cessna 310 type certificate were required to show the fuel amount in US gallons. An exemplar is shown in Figure 2.

Figure 2: Correct aircraft fuel selector plaques

Figure 2: Correct aircraft fuel selector plaques

Source: Nimbus Aviation, modified by the ATSB

VH-JQK’s fuel selector plaques showed fuel quantities in differing units (Figure 3). On the left plaque only, an indication of fuel tank capacity was handwritten in white permanent marker with the quantities in litres. The right plaque had what appeared to be original markings from an aircraft with different auxiliary tank capacity. The left auxiliary tank was indicated as having a capacity of ‘70 Ltr’ (70 L, equivalent to 18.5 gallons), corresponding to the smaller auxiliary tank capacity (as was fitted to VH-JQK). The right plaque gave that side’s auxiliary tank capacity as ‘31.5 GAL’ (31.5 gallons, or 119.3 litres), corresponding to the larger auxiliary tank capacity.

The ATSB was not provided the aircraft logbooks or maintenance releases to confirm when the modification of the plaques, both the incorrect right-side plaque and handwritten quantities, took place.

Figure 3: VH-JQK fuel selector plaques

Figure 3: VH-JQK fuel selector plaques

Source: Operator, annotated by the ATSB

Fuel gauges

The fuel quantity gauge (Figure 4) was located above the right side control column and normally indicated the fuel quantity (in both gallons and pounds) in the selected tanks. The fuel quantity in the non-selected tanks could be displayed instead through the use of a momentary toggle switch below the gauge. Two yellow lights (one for each side) illuminated when the auxiliary tank on that side was selected.

Figure 4: Fuel gauges in VH-JQK

Figure 4: Fuel gauges in VH-JQK

Source: Operator, annotated by the ATSB

Pilot’s operating handbook

The operator used 2 versions of the pilot’s operating handbook (POH):

  • a generic softcopy version
  • a hardcopy which was carried in the aircraft.

The softcopy POH included multiple aircraft serial numbers and inconsistent registration details throughout the document, none of which matched VH-JQK. This version of the POH did not indicate the fuel tank configuration of VH-JQK.

The POH carried in the aircraft included an aircraft flight manual approval from the Civil Aviation Safety Authority, but the approval did not specify the serial number of the approved aircraft. The POH was not specific to VH-JQK’s particular configuration (showing the 6 possible fuel tank configurations available for Cessna 310R aircraft) but had handwritten markings indicating VH-JQK’s fuel system configuration (Figure 5).

Figure 5: Pilot’s operating handbook carried in VH-JQK

Figure 5: Pilot’s operating handbook carried in VH-JQK

Source: Operator, annotated by the ATSB

The Federal Aviation Administration (FAA) Pilot’s Handbook of Aeronautical Knowledge (2022)[8] stated that while the POH may appear similar for different aircraft of the same make and model, each manual should be unique and contain specific information about a particular aircraft, such as the equipment installed and the weight and balance information. If a manual does not indicate a specific registration and serial number, it should be limited to general study purposes only. The online POH did not accurately indicate the installed fuel tanks in VH-JQK and due to multiple serial numbers through the manual, the document was unable to support pilot understanding of specific differences with VH-JQK.

The POH recommended to use fuel from the main tanks during both take-off and landing (for aircraft fitted with 40-gallon auxiliary tanks).

The POH stated that when all fuel tanks were full, the main tank fuel should be used after take-off for about 60 minutes or until 180 lb (102 L) or less is remaining. Auxiliary tanks should then be selected. This was necessary to provide space in the main fuel tanks for vapour and unused fuel to be returned from the engine driven fuel pumps when operating on auxiliary fuel.

If sufficient space was not available in the main tanks for this diverted unused fuel, the main tanks could overfill, and fuel could be lost out of overboard fuel vents. It was recommended that auxiliary fuel was used until either exhausted or the flight phase had reached the top of descent.

At the time of the occurrence the trainee instructor reported that they did not fully know that excess fuel was returned to the main fuel tanks when the auxiliary tanks were selected. The trainee instructor reported they had relied on the instructor to know the differences in the fuel system.

Operator’s operations manual

The operator’s operations manual outlined the entire fleet of aircraft operated by the company. The only Cessna 310 data sheet available in the operations manual was for a Cessna 310H, which had significantly different performance and fuel system characteristics. The operations manual did not contain information on fuel tank availability and capacity for VH-JQK, the Cessna 310R or the 310H.

In the flight planning section of the operations manual, a generic fuel flow rate was provided fora generic Cessna 310 and did not identify a specific model. The flight planning fuel flow rate was of 100 L/hour.

The data sheet section of the operations manual identified the Cessna 310H has a fuel flow rate of 90 L/hour, while the operator’s cross hire list, also found in the operations manual, detailed the Cessna 310R as having a fuel flow of 120 L/hour. The typical cruise fuel flow rate of the Cessna 301R is about 117 L/hour.

Operator fuel management procedures

Pre-flight

The operator’s operation manual required the pilot in command (in this case, the instructor) ensure that a determination of the quantity of usable fuel on board was conducted before flight. Fuel quantity gauge readings were to also be cross-checked, to ensure accurate fuel calculation against one of the following:

  • visual confirmation – full, tabs or dipstick reading
  • calculated – a comparison of the fuel on board from the previous flight with fuel added with reference to the operator’s aircraft journey log form (Figure 6).

Figure 6: Operator aircraft journey log

Figure 6: Operator aircraft journey log

Source: Operator

Should a pilot identify any significant discrepancy between the actual and calculated quantities, this was required to be reported to maintenance engineer staff for further investigation.

This fuel log was generic for the operator’s fleet and did not distinguish between the contents of the main fuel tanks and the auxiliary fuel tanks for the Cessna 310R. The log did not indicate which units should be used.

The aircraft journey log was requested by the ATSB for the investigation; however, the operator was unable to locate and produce the document.

In-flight

The operator’s operations manual stated:

During all flights, at a 30-minute interval, our pilots conduct a fuel quantity check whereby the usable fuel remaining is evaluated to compare planned fuel consumption with actual fuel consumption. This is accomplished by cross-referencing the fuel remaining on gauges with an appropriately calculated fuel log covering aircraft endurance – litres and minutes of fuel remaining. Our pilots determine the expected usable fuel remaining on arrival at the destination aerodrome and whether the usable fuel remaining is sufficient to complete the planned flight.

Post flight

Upon return from a flight, pilots were required to complete the fuel documentation including the journey log with the amount of fuel at shutdown.

Related occurrences

Fuel management and fuel starvation incidents and accidents continue to occur in twin engine aircraft. Examples of ATSB investigations of these include:

  • Fuel starvation and forced landing involving Piper PA-28, VH-BDB, 15 km WSW of Bankstown Airport, NSW, on 19 September 2017 (AO-2017-094AO-2017-094)
  • Fuel starvation involving Cessna 206, 3.5 NM NE of Aldinga, SA, on 3 February 2019
    (AB-2019-004)
  • Cessna C310R, VH-HCP, 3km E Newman Aerodrome on 26 January 2001 (200100348)

The ATSB found that pilot understanding of, and management of aircraft fuel systems played a crucial role in these occurrences.

The 2013 ATSB publication, Avoidable Accidents No. 5: Starved and exhausted: Fuel management aviation accidents (AR-2011-112) focused on accidents involving fuel starvation due to fuel management, stating:

Keeping fuel supplied to the engines during flight relies on the pilot’s knowledge of the aircraft’s fuel supply system and being familiar and proficient in its use. Adhering to procedures, maintaining a record of the fuel selections during flight, and ensuring the appropriate tank selections are made before descending towards your destination will lessen the likelihood of fuel starvation at what may be a critical stage of the flight.

Safety analysis

Overview

Surging can be a result of a piston engine being starved of fuel. In this case, the crew observations of surging and fuel streaking from the main tanks during and after the flight were consistent with the main tanks being full and the auxiliary tanks being empty. Once the fuel selectors were switched to the main tanks, the engines recovered. The surging was therefore almost certainly caused by the auxiliary fuel tanks emptying while selected during the flight.

After departure, the crew operated for about 30 minutes with the main fuel tanks selected before changing to the auxiliary tanks. At a fuel flow rate of 120 L/hour, the engines would have used about 120 L at the time the surging began. This alone would not have been enough to empty the auxiliary tanks, which held about 140 L; however, in this aircraft, unused fuel from the fuel pumps would also be transferred from the auxiliary tanks to the main tanks.

This would have reduced the quantity of fuel in the auxiliary tanks at a faster rate than just engine consumption in the period between switching to auxiliary tanks and the engine surging. This would explain why the auxiliary tanks were exhausted of fuel. In addition, the main tanks became full during this period and excess fuel was lost overboard through venting.

The auxiliary tanks continued to be used until they became exhausted, resulting in fuel starvation and engine surging. This analysis will examine the reasons for this fuel starvation, the crew’s management of fuel throughout the flight, and the information provided by the operator for pilots to manage fuel.

Fuel management

The operator was unable to locate the aircraft journey log and the fuel on board prior to the occurrence could not be determined. Operator requirements detailed that the fuel on board at the start of the flight were to be recorded in the aircraft journey log. However, this was not done. This journey log was intended to indicate the amount of total fuel left on board the aircraft from the previous flight and be used as a basis for planned versus actual fuel usage for the flight. The journey log would not have given the pilots an exact indication as to how much fuel was left in each tank.

The aircraft journey log, the fuel gauges and the dipstick readings were available to cross-check the fuel quantities to allow highest level of certainty of the amount of usable fuel onboard.

The interval between in-flight fuel quantity checks of 30 minutes was set out by the operator to prompt pilots to remain aware of the aircraft fuel state. The trainee instructor was uncertain as to why the tanks were changed from main to auxiliary after 30 minutes, earlier than the normal 60 minutes outlined in the POH, and both crew were unable to recall the fuel gauge quantity throughout the flight. This indicates that it was likely the crew were not checking the fuel gauges every 30 minutes.

Post flight inspection indicated that although the auxiliary tanks were empty, the main tanks were completely full. The aircraft was able to be flown back to Redcliffe without issue, this indicated that the total amount of usable fuel on board was sufficient for the planned flight.

The pilots did not completely follow operator’s pre-flight and in-flight fuel management procedures including keeping a fuel log, cross-checking the amount of fuel on board, and tracking fuel quantity throughout the flight. This resulted in the pilots continuing to select fuel from the auxiliary tanks beyond the point when they were empty and subsequently the starvation of both aircraft engines.

Familiarity with the aircraft fuel system

The instructor was not familiar with the fuel capacity of VH-JQK. The auxiliary fuel tank capacity was significantly lower than other previous Cessna 310R aircraft the instructor had operated. They had assumed that the auxiliary tanks held about 100 L more than VH-JQK could.

The trainee instructor relied on the instructor’s experience on the Cessna 310 aircraft and had limited experience of the aircraft and fuel system. Familiarisation with the aircraft’s fuel system should have been completed prior operating the aircraft and not relied solely on the instructor’s previous experiences.

Aircraft fuel system documentation

The data sheets which were provided in the operator’s operations manual did not provide the correct information about the current Cessna 310 variant being flown by the operator and instead provide a generic fuel flow rate for the C310.

There was no clear information set around the Cessna 310R fuel flow rates or fuel tank configuration within the operations manual. Effective fuel planning and fuel management rely on the accuracy of the predicted fuel consumption rate. With 3 different fuel flow rates outlined in the operations manual, the inconsistent data impedes the accuracy of the of the fuel consumption data used for planning and decision-making.

These fuel flow rates were recorded in L/hour yet the fuel quantity for the Cessna 310R was variously measured in gallons, litres and pounds. Accurately calculating and managing fuel is a critical aspect of safe aircraft operation. Using different units of measurement for fuel calculation and management can introduce unnecessary complexity and lead to errors.

For example, converting units can make it more difficult to cross-check the fuel levels and detect fuel discrepancies or leaks. It was not possible to determine whether this was a factor in the occurrence, however, it can lead to difficulties in remembering and calculating fuel quantities.

The hardcopy POH incorrectly indicated that there was a nacelle tank installed. Clear information about the capacity and usability of the nacelle tanks was not provided to pilots and students.

Fuel selector plaques

The fuel selector plaques were incorrectly labelled. The left plaque provided the incorrect unit of measure, and the right plaque provided the incorrect size of auxiliary tanks available. 

The ATSB determined that the fuel selector plaques did not contribute to the occurrence as both the instructor and student instructor did not recognise the inconsistent markings on the selector. However, inconsistent and incorrect markings have the potential to cause pilots to inadvertently make incorrect fuel calculations.
 

Findings

ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.

These findings should not be read as apportioning blame or liability to any particular organisation or individual.

From the evidence available, the following findings are made with respect to the fuel starvation event involving Cessna 310, VH-JQK, near Sunshine Coast Airport, Queensland, on 18 August 2022.

Contributing factors

  • The pilots did not establish the amount of fuel on board prior to the flight or manage the fuel state throughout the flight.
  • The instructor was not aware that the aircraft had a 140L usable fuel auxiliary tank capacity and assumed that it had the same 238L capacity as other Cessna 310 aircraft they had flown.

Other factors that increased risk

  • The operator had inconsistent and incomplete technical documentation for the aircraft.
  • The aircraft’s fuel selector plaques contained contradictory and incorrect information about the capacity of the auxiliary tanks, and in different units.

Safety actions

Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.

Safety action by Aircraft Australia

After an internal investigation, Aircraft Australia implemented a new fuel log specific for the Cessna 310R. They have released an internal memo for the company operations manual outlining the changes to the data sheet for the Cessna 310R to ensure all pilots and student are aware of the fuel configuration of the aircraft. The operator has also requested fuel selector plaques replacement to ensure the correct data labels are installed.

Sources and submissions

Sources of information

The sources of information during the investigation included:

  • the instructor and trainee instructor of the occurrence flight
  • Aircraft Australia
  • Flightradar 24.

Submissions

Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.

A draft of this report was provided to the following directly involved parties:

  • Civil Aviation Safety Authority
  • instructor and trainee instructor of VH-JQK
  • Aircraft Australia.

Submissions were received from:

  • Civil Aviation Safety Authority.

The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.

Purpose of safety investigations

The objective of a safety investigation is to enhance transport safety. This is done through:

  • identifying safety issues and facilitating safety action to address those issues
  • providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.

It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.

Terminology

An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.

Publishing information 

Released in accordance with section 25 of the Transport Safety Investigation Act 2003

Published by: Australian Transport Safety Bureau

© Commonwealth of Australia 2023

image_5.png

Ownership of intellectual property rights in this publication

Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.

Creative Commons licence

With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.

Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.

The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau

Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.

[1]     Cross-checked: The use at least two different verification methods to determine the amount of fuel on board.

[2]     Under the hood: Indicates that the pilot is using a hood to restrict visibility outside the cockpit while simulating instrument flight. An appropriately rated pilot is required in the other control seat while this operation is being conducted.

[3]     Instrument meteorological conditions (IMC): weather conditions that require pilots to fly primarily by reference to instruments, and therefore under instrument flight rules (IFR), rather than by outside visual reference. Typically, this means flying in cloud or limited visibility.

[4]     Flaps: movable surfaces on the trailing edge of the wing that help the aircraft gain lift.

[5]     Fuel venting: the process of releasing excess fuel vapours from the fuel tanks of an aircraft.

[6]     Yawing: the motion of an aircraft about its vertical or normal axis.

[7]     Runway number: the number represents the magnetic heading of the runway in the nearest tens of degrees. The runway identification may include L, R or C as required for left, right or centre.

Occurrence summary

Investigation number AO-2022-040
Occurrence date 18/08/2022
Location 2 NM east of Sunshine Coast Airport
State Queensland
Report release date 05/05/2023
Report status Final
Investigation level Short
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Engine failure or malfunction
Occurrence class Serious Incident

Aircraft details

Manufacturer Cessna Aircraft Company
Model 310R
Registration VH-JQK
Serial number 310R1355
Aircraft operator AIRCRAFT AUSTRALIA PTY LTD
Sector Piston
Operation type Part 141 Recreational, private and commercial pilot flight training
Departure point Redcliffe Airport, Queensland
Destination Redcliffe Airport, Queensland
Damage Nil