Airbus A320-211, VH-HYO, Adelaide Aerodrome, South Australia, on 20 August 1999

Safety Action

Local safety action

As a result of this occurrence, the BoM's analysis and report of the meteorological aspects of the occurrence included the following recommendations:

  1. As BoM's observation stations at Parafield and Edinburgh will be closed before the winter of 2000, BoM should consider installation of a "Skycam" on a city building to better appreciate the extent of fog and low cloud when the conditions that led to this occurrence are present. In addition, BoM should urgently consider a research project on guidance material for prediction of fog events at Adelaide and Edinburgh airports.
  2. As BoM's observing site is poorly located at Adelaide Airport in reference to fog and low stratus cloud to the north of the airport, BoM should consider relocation of the site to eliminate this impediment.
  3. BoM should conduct a workshop for local forecasters on fog events and local guidance before the winter of 2000.

On 16 December 1999, BoM reported:

  1. BoM was considering "Skycam" installations on a national basis, expecting that trials would be conducted in the eastern states due to higher traffic levels.
  2. The relocation of the BoM's observation site at Adelaide Airport was included in the airport upgrade. In addition, a radio was installed in the BoM's airport office enabling forecasters to monitor the Automatic Terminal Information Service (ATIS) from Adelaide, Parafield and Edinburgh.
  3. Research and workshops were an ongoing requirement in BoM, but depend upon staff availability.

On 19 July 2000, BoM reported:

  1. BoM assessed the range of Skycam units available and obtained the agreement of the aviation industry to fund the installation of one unit at a major airport (not Adelaide). The industry has undertaken to assess the value of the information obtained from that unit before making any decision on possible funding of further units.
  2. The BoM offices at RAAF Edinburgh and Parafield closed in December 1999. Since those closures, an automatic weather observation station was installed and has been operating at RAAF Edinburgh. The tower controllers at Parafield have also been providing some observations.
  3. The relocation of the BoM office at Adelaide Airport was scheduled for December 2000, but could be delayed until early 2001. The proposed new site for the office was closer to the runways than the present office and was expected to provide better views of fog areas and low cloud than were available from the present site.
  4. It has not been possible to hold workshops due to staffing limitations.

Summary

As the aircraft approached runway 23 for landing, the crew observed a bank of fog drifting toward the aerodrome from the north-east. By the time the aircraft arrived at the aerodrome, the runway threshold was obscured by the fog. As a result, the crew elected to conduct a missed approach.

During the missed approach, the crew noticed that the threshold area of runway 05 was clear, so they requested an immediate visual approach to runway 05 before the fog drifted further to the south-west. Due to other instrument flight rules traffic, Air Traffic Control (ATC) could not issue an immediate clearance for the approach. By the time that clearance was available, the remainder of the runway was obscured by fog. A B737 aircraft had been able to land on runway 05 following a VOR/DME approach, so the A320 crew attempted to conduct a similar approach. However, that attempt resulted in a second missed approach. The aircraft tracked to the north-east of the aerodrome and the crew informed ATC that they would conduct an instrument landing system (ILS) approach to runway 23, and then land using the aircraft's autoland system. With 1,500 kg of fuel remaining, the aircraft landed without incident in the fog. Visibility was 250 to 350 m.

The aircraft was certificated for autoland approaches, but the ground equipment was not. The ILS transmitter was a Category 1 unit with a minimum visibility of 1,200 m required for landing. The crew decided to conduct an autopilot-coupled approach with automatic landing, as fog was also present at the Royal Australian Air Force base at Edinburgh, rendering that aerodrome unsuitable as an alternate. The crew considered that Whyalla, the nearest suitable aerodrome, was likely to have similar weather conditions to Adelaide.

Fog had not been forecast for Adelaide when the crew submitted their flight plan. Consequently, the aircraft did not carry fuel for holding at Adelaide or for diversion to an alternate.

However, fog had been forecast for both Edinburgh and Parafield. The Bureau of Meteorology (BoM) reported that this was not unusual, as records showed that in the past 20 years, fogs formed at both Adelaide and Edinburgh on about 50% of occasions, with Edinburgh proving to be the greater risk. On the day of the occurrence, moisture levels were higher to the north of Adelaide, with fog forming at Edinburgh at 0700 Central Standard Time. What was unusual about this event was that the advection of fog from the north took place at a greater speed than the surface wind and that the onset time of fog at Adelaide Airport was 40 minutes later than any recorded onset time at that location in the past 30 years.

BoM records showed that Adelaide Airport averaged 4.9 fog events per annum. The highest annual total for events was nine, recorded in both 1956 and 1983. At the time of the incident on 20 August, there had been 11 fog events recorded at Adelaide Airport during 1999.

Occurrence summary

Investigation number 199904029
Occurrence date 20/08/1999
Location Adelaide, Aero.
State South Australia
Report release date 28/08/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Airbus
Model A320
Registration VH-HYO
Serial number 547
Sector Jet
Operation type Air Transport High Capacity
Departure point Melbourne, VIC
Destination Adelaide, SA
Damage Nil

Piper PA-28-140, VH-CNM, on 3 September 1999

Summary

The crew of a SAAB, conducting a scheduled passenger service from Griffith to Sydney, broadcast that they were taxiing to depart from runway 06. The pilot of a Cherokee advised that he was on downwind for runway 36. The crew acknowledged this transmission and then established the position and intentions of the pilot of a Dromader who was on an extended downwind leg for a low-level approach to runway 06. The crew of the SAAB then advised that they were entering and backtracking on runway 06. Approximately 90 seconds later, when the crew advised they were rolling on runway 06, the pilot of the Cherokee responded that he was on late finals to runway 36. The crew continued their take-off and overflew the landing Cherokee by a reported 400 feet.

Each aircraft was in radio communication on the Griffith common traffic advisory frequency of 126.7 MHz.

The crew of the SAAB later reported that they had not heard the pilot of the Cherokee respond to their taxiing broadcast. Their attention had been directed toward the pilot of the Dromader who had adjusted his approach to assist their departure. They had not seen the Cherokee and consequently it was not until the pilot reported on late finals to runway 36 that they realised there was a traffic conflict. The crew reported that at this time the SAAB had accelerated to a speed such that rejecting the take-off was potentially more hazardous than continuing.

The higher terrain to the south of the aerodrome may have made the Cherokee more difficult to detect against the background. Additionally, a line of trees to the south of runway 06 obscured the final approach path to runway 36 from the view of pilots at the 06 threshold.

The reason why the crew of the SAAB did not recall hearing the response of the Cherokee pilot to their taxiing report was not determined. However, it is likely that the decision to expedite their departure ahead of the arriving Dromader created a self-imposed high workload that led to a loss of awareness of the Cherokee.

Occurrence summary

Investigation number 199904284
Occurrence date 03/09/1999
Location Griffith, Aero.
State New South Wales
Report release date 28/02/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Separation issue
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Piper Aircraft Corp
Model PA-28
Registration VH-CNM
Serial number 28-7725045
Sector Piston
Operation type Flying Training
Departure point Griffith, NSW
Destination Griffith, NSW
Damage Nil

Aircraft details

Manufacturer Saab Aircraft Co.
Model 340
Registration VH-CMH
Serial number 327
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Griffith, NSW
Destination Unknown
Damage Nil

Boeing 737-377, VH-CZB, Sydney Aerodrome, New South Wales, on 9 August 1999

Safety Action

As a result of this incident and chafing found on the galley connectors of another B737 aircraft, the operator issued Engineering Release E/R B73-24-00-22 on 30 September 1999. This required the operator to inspect all B737 aircraft for chafed or burnt wiring on the galley power connectors and to reinstall insulation tape if required. The inspection showed that four other aircraft needed to have the galley connector wiring insulation retaped with none exhibiting any chafed or burnt wiring damage.

Abstract

Performance monitoring of the auxiliary power unit (APU) was being carried out during ground maintenance of the Boeing 737-300. Maintenance staff reported that the electrical system voltage had surged twice and that the aircraft interior lights had dimmed before voltage and frequency indications returned to normal. No circuit breakers had tripped. When maintenance personnel in the aircraft cockpit noticed a burning smell, they shut down the APU to investigate the fault.

The forward No. 2 galley ovens were found to be inoperative. During further troubleshooting, ground power was applied twice, which resulted in smoke emanating from a ceiling access panel above the forward No. 2 galley assembly.

The fault was traced to the electrical connector supplying 115VAC three-phase power to the forward No. 2 galley ovens. The connector and associated wiring behind an overhead panel were burnt. The seven-pin connector had a five-wire bundle comprising phases A, B, C, neutral D and static ground. The three-phase wires had desoldered from the pins on the connector. Arcing damage was found on the endbell and cable clamp halves of the connector.

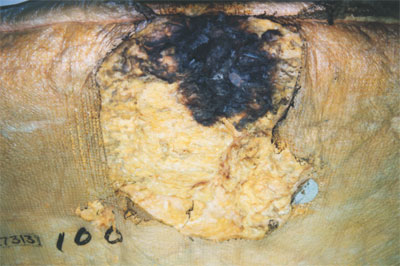
The insulation blanket and galley panels next to the connector were blackened and heat-damaged. Charring of the insulation material had occurred over an area of about 75 mm x 100 mm. The film covering the blanket had burnt for a further 150 mm to 250 mm.

Figure 1: VH-CZB damaged insulation blanket

Figure 1: VH-CZB damaged insulation blanket

The galley manufacturer and operator established that arcing and heating of the connector and wiring was due to inadequate soldering and insertion of the phase wires into the connector-pin buckets. Only the static ground-wire connection was found to meet the manufacturer's soldering process standard.

The connector at the other end of the damaged cable was also examined. The solder terminations of phases A, B, C and neutral D were also found to be substandard, with solder smeared on the outside of the contact pin wall and only a small amount of solder bonding the cable strands to the contact pin.

The phase and neutral wire-identification numbers stamped on the insulation were of a different size and orientation from those supplied by the galley manufacturer (as shown on the static ground wire insulation). The wire-identification number stamps matched those held by the operator.

The arcing damage found on the endbell and cable-clamp halves of the connector had no matching wire-bundle insulation damage, showing that the damage had occurred before this incident. The resulting damage to the cable probably explains why the phase A, B, C and neutral D wires had been replaced and re-identified.

Forward No. 2 galley was the original fitment on this aircraft, delivered in September 1986. The operator reported that disconnection of the subject connector would occur only during scheduled galley removal at each D-check. The sole D-check on this aircraft occurred in July 1994. The operator reviewed maintenance and pilot discrepancies raised against electrical power and galley equipment systems since aircraft delivery, but did not find any failures requiring loom replacement. Similarly, a review of D-check work documents showed no galley electrical system discrepancies.

The insulation blanket and film-like covering from above the forward No. 2 galley were heat damaged as a result of the electrical connector fault. The operator reported that the blanket-covering material (Orco Film AN-26) did not appear to be flame retardant to the level of FAR 25.853. The operator believed that the accumulation of organic material on the surface of the film over 13 years, especially corrosion inhibiting compound mist, would have changed the film's flammability performance. As a result of the accident involving Swissair flight 111, the U.S. Federal Aviation Administration is researching the flammability of thermal acoustical insulation materials.

Occurrence summary

Investigation number 199903995
Occurrence date 09/08/1999
Location Sydney, Aero.
State New South Wales
Report release date 14/09/2001
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 737
Registration VH-CZB
Serial number 23654
Sector Jet
Operation type Air Transport High Capacity
Damage Minor

Fokker B.V. F27 MK 50 , 20107, VH-FNB, 130 km south of Carnarvon (VOR), Western Australia, on 6 August 1999

Safety Action

The key factors involved with this incident are common to other incidents investigated by the Bureau and which were the subject of safety recommendation R19990220 issued by the Australian Transport Safety Bureau (formerly BASI) to Airservices Australia on 19 January 2000.

Local safety action by Airservices Australia

Airservices Australia advised the ATSB that the existing flight service operations will continue until early 2001 when the national program of incorporating directed traffic information into TAAATS will be completed. Airservices is aware of the need to be vigilant in the management of this change process.

Analysis

FNB should have been reported as potential traffic to the crew of FNA since its track was planned to be within 15 NM laterally of FNA's route and because it was climbing through FNA's level.

The flight service officer reported that he would have normally passed traffic information to the pilots when FNB taxied at Carnarvon. However, on this occasion, he did not recognise that the two aircraft were potentially conflicting traffic. Having calculated a release time of 0225 when he expected FNB to be above FL200, in controlled airspace and therefore clear of FNA, he may have assumed that the traffic had no potential for conflict. An indication of his assumption was that he filed the flight strip for FNB soon after the release time; therefore, the potential for conflict of these two aircraft was never recognised by the flight service officer.

The flight service officer did not have a history of inadequately passing appropriate traffic information although he had, on occasion, used inappropriate air traffic control procedures.

The incident probably occurred as a result of a combination of factors. Firstly, the flight service officer reported that he was pre-occupied with his personal situation and was tired. As a result, he probably did not adequately monitor the progress of his routine actions. Secondly, he reported that he might have used a presumed rate of climb for the Fokker 50 as a basis for determining whether the traffic was potentially conflicting. Such a calculation was erroneous and irrelevant because the traffic assessment criteria in the Manual of Air Traffic Services required the traffic information to be passed. The use of this calculation may have been a manifestation of the flight service officer's occasional use of inappropriate procedures. His pre-occupation, tiredness and deviation from standard operating procedures may have contributed to the flight service officer losing situational awareness and as a result, he did not recognise that the flight paths of FNB and FNA were potentially conflicting.

Once the flight service officer had committed to not advising the crews of FNB and FNA of each other's presence, there were no organisational defences available, such as active supervision, to preclude the mistake going unnoticed. As a result, once the flight service officer had made the error, there was no backup.

Because the pilot in command of FNB did not need to take any avoiding action, it is unlikely that the provision of TCAS stopped an accident from occurring. However, the fact that TCAS had alerted the crew of FNB to the close proximity of traffic unknown to them indicated that it would have been the only defence available had the two aircraft been on a collision course. The effectiveness of TCAS in alerting and directing the crew of FNB to proximal traffic also illustrated the weakness of the principle of see-and-avoid.

CONCLUSION

The flight service officer was fatigued and distracted, probably as a result of stress and inadequate rest before commencing his shift. Consequently, he did not adequately monitor the progress of his routine actions and he did not notice that the two aircraft were potentially conflicting traffic. He did not provide traffic information to the pilots of the two aircraft as required by Manual of Air Traffic Services.

Summary

Sequence of events

At 0208 coordinated universal time (UTC) VH-FNB, a Fokker 50, departed Carnarvon for Perth southbound via air route B469 and was climbing to FL210. The two-way air route was a direct track between Carnarvon and Geraldton . VH-FNA, also a Fokker 50, had departed Geraldton for Learmonth and was tracking via the B469 northbound. The crew of FNA had reported to Perth Flight Service at 0201 that the aircraft was on descent to FL180 from FL200. At 0213, they reported at position HAMEL and were estimating overhead Carnarvon at 0246. HAMEL was a reporting point located 120 NM south-south-east of Carnarvon. FNB's estimated time of arrival at HAMEL was 0242.

About 65 NM south-south-east of Carnarvon and approaching FL180, the co-pilot of FNB glanced down at the traffic alert and collision avoidance system (TCAS) display and noticed a return in the 11-o'clock position at about 7 NM at the same level. The pilot in command of FNB, aware that FNA was likely to be in the area, communicated with the crew of FNA and requested their position. At 0226, as the pilot in command of FNA replied, the pilot in command of FNB saw FNA pass approximately 400 ft below his aircraft on a reciprocal track. FNA was not fitted with a TCAS and the crew of FNA did not see FNB. Flight service had not directed traffic information to either crew.

Flight Service procedures

Both aircraft were outside controlled airspace and operating in a directed traffic information environment in which air traffic control does not provide positive separation between air traffic. However, flight service was required to provide aircraft operating under instrument flight rules information on other possibly conflicting military or instrument flight rule traffic. The requirements and parameters for issuing traffic advice by flight service are in the Manual of Air Traffic Services. The procedures in the manual required the flight service officer to provide traffic information to the crews of both FNA and FNB about each other's flight routes because both aircraft were going to be within 15 NM of each other laterally and FNB was climbing through FNA's level.

When aircraft are planned to depart non-controlled airspace and enter controlled airspace, the flight service officer calculates a release time, which is the time at which the flight service officer expects the pilot of the aircraft to be communicating with air traffic control. When air traffic control receives notification from flight service that an aircraft will be entering controlled airspace, the controller calculates a time of acceptance when the aircraft is expected to be on frequency. Neither the release nor acceptance times are coordinated between flight service and air traffic control.

Flight Service Officer actions

The flight service officer was managing the combined sectors of Flight Service 1 and 8 at the time of the incident. Flight service team leaders were responsible for the administration of shifts. They did not provide active supervision of flight service officers at their work positions.

At the time of the incident, the flight service officer was responsible for monitoring 13 VHF and 8 HF frequencies, and 15 aircraft. Of the 15 aircraft, approximately 10 were active and the remainder were pending. Consequently, the flight service officer and his supervisor reported that the workload was considered light to moderate.

The flight service officer reported that he had assessed that after departure it would take FNB 15 minutes to climb through FL200 into controlled airspace. He therefore calculated that FNB would be in controlled airspace at about 0223 and he rounded up his expected release time to 0225. Air traffic control reported that they added a standard 15 minutes to the departure time advised unless the aircraft was known to have a low performance climb, such as the Fokker 50. In this case, 20 minutes was added. Therefore, the expected on-frequency time for FNB would have been 0228 and in accordance with standard practice, communications checks would have commenced by 0231.

The flight service officer reported that he would have normally passed traffic information to the pilots of both aircraft when FNB taxied at Carnarvon. The flight service officer was unable to explain why he did not believe the two aircraft were potentially conflicting. Following the incident, the flight service officer reported that he thought the Fokker 50 would have climbed at about 1,500 ft/min, a figure he reportedly derived from a previous conversation with one of the operator's pilots. Advice from the operator indicated that it was highly unlikely that a Fokker 50 could achieve such a rate-of-climb, particularly at the flight levels at which FNB was operating. The local flight service management reported that flight service did not advocate calculations based on rate of climb as a traffic assessment method.

The flight service officer reported that he filed the flight strip for FNB soon after the release time of 0225, believing the aircraft to be clear of non-controlled airspace.

Human factors

The flight service officer had received some air traffic control training and reported that he had previously used air traffic control techniques to determine whether traffic was in potential conflict. The use of air traffic control techniques was not required or advocated in flight service procedures. The flight service officer had passed a performance check the day before, when the checking officer noted him using some air traffic control procedures to decide what traffic information should be provided. The supervisor counselled him at the time not to use such procedures. The flight service officer reported that he had been using air traffic control techniques for some time to determine what information needed to be passed to aircraft operating outside controlled airspace in an attempt to reduce the amount of, what he considered, unnecessary radio calls. Although the flight service officer had used unapproved procedures in the past, he did not have any history of providing inadequate or inappropriate traffic information. During the investigation, it was reported that other flight service officers who had undergone some air traffic control training were also known to have applied air traffic control procedures in the flight service environment.

The flight service officer reported that Airservices Australia had managed his career within the previous 2 years in such a manner that caused him concern because there was substantial uncertainty related to his future employment. The flight service officer also reported that as a result of this uncertainty, he was facing significant personal issues and was probably pre-occupied by these issues when he started the shift on the day of the incident. He had approached his local management prior to the incident for leave and the request was being processed at the time of the incident.

The flight service officer reported that he was uncertain about his future employment and as a result of this uncertainty he had only a small amount of sleep the night before his shift and was feeling tired at the time of the incident. The flight service officer's immediate supervisor reported that he was unaware that the flight service officer may have been experiencing significant personal stress or that the flight service officer was fatigued when he commenced duty.

Traffic alert and collision avoidance system

Both aircraft belonged to the same operator. The operator was introducing TCAS as each aircraft underwent a major servicing. FNB was the only aircraft in the operator's fleet that had been fitted with TCAS and not all of the operator's pilots had been trained in the use of TCAS. The operator's policy was that unless both pilots in a crew were qualified to use TCAS, then the equipment was only to be used in the traffic advisory (TA) mode. A TA is indicated on the equipment display to the crew when the aircraft are within about 48 seconds of their closest passing, based on projections derived from current flight path and speed.

Occurrence summary

Investigation number 199903790
Occurrence date 06/08/1999
Location 130 km S Carnarvon, (VOR)
State Western Australia
Report release date 24/03/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Separation issue
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Fokker B.V.
Model F27
Registration VH-FNB
Serial number VH-FNB
Sector Jet
Operation type Air Transport High Capacity
Departure point Carnarvon, WA
Destination Perth, WA
Damage Nil

Aircraft details

Manufacturer Fokker B.V.
Model F27
Registration VH-FNA
Serial number VH-FNA
Sector Jet
Operation type Air Transport High Capacity
Departure point Geraldton, WA
Destination Carnarvon, WA
Damage Nil

Sikorsky S-76A, VH-BHM, Barrow Island Aerodrome, Western Australia, on 4 August 1999

Safety Action

Operator safety action

The operator issued an alert message for its fleet of S76 helicopters to undergo an inspection of the subject area. A defect report was also submitted to the Civil Aviation Safety Authority.

Manufacturer safety action

As a result of this incident and a similar incident experienced by another Australian S76 operator in 1995, and following consultation between the operator, helicopter manufacturer and BASI; the manufacturer conducted a design engineering review of the cyclic stick base hardware to determine if it was possible to reduce the effect of foreign object entry to the tub area.

Following the review, the manufacturer advised that a field modification of the pilot's side bracket was being prepared to increase the gap between the torque tube rig boss and the bracket foot. On 28 August 1999, the manufacturer also advised of its intention to issue an Alert Service Bulletin, in due course, to address the results of the engineering review.

BASI safety action

BASI will monitor the progress of this manufacturer's proposed safety action.

Summary

The pilot of the Sikorsky S76 helicopter reported that while approaching Barrow Island and immediately after he reduced the helicopter's airspeed for landing gear extension, he found that the cyclic could not be moved aft. He also found that with any further forward movement of the cyclic stick, the stick then could not be moved aft of the new position. The pilot froze the cyclic longitudinal position and the helicopter stabilised in a level pitch attitude at about 85 kts indicated airspeed. Using only lateral cyclic movements to manoeuvre the helicopter, the pilot conducted an 80-kt run-on landing on the runway at Barrow Island.

The subsequent maintenance inspection found a panhead type screw at the base of the cyclic stick. The screw had lodged between the lower protrusion on the casting on the end of the cyclic stick torque tube and the lugs on a support bracket. The lodgement of the screw in that location had caused the cyclic restriction experienced by the pilot.

The cyclic stick base hardware was accommodated in a tub-like area formed by the cabin structure supports. A leather boot mounted at the base of the cyclic normally prevented foreign objects from entering the tub. The subsequent maintenance inspection found the leather boot on this helicopter to be intact. With the boot in place, the only possible entry points where a screw could be inserted was through a rigging pin hole in the aft mid-height position of the boot-halves joint, or vertically through an opening provided for the cyclic stick electrical wiring loom. Due to the unlikelihood that a screw could enter the tub area when the boot was fitted, the screw was probably introduced to the area during prior maintenance while the boot was removed.

Occurrence summary

Investigation number 199903789
Occurrence date 04/08/1999
Location Barrow Island , Aero.
State Western Australia
Report release date 20/10/1999
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Control - Other
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Sikorsky Aircraft
Model S-76
Registration VH-BHM
Serial number 760107
Sector Helicopter
Operation type Charter
Departure point Cossack Pioneer, WA
Destination Barrow Island, WA
Damage Nil

Fairchild SA227-DC, VH-DMO, 2 km north-north-east of Latrobe Valley Aerodrome, on 25 July 1999

Safety Action

As a result of this occurrence, the Australian Safety Transport Bureau is currently investigating a safety deficiency relating to procedures allowing straight-in approaches to be flown at aerodromes where there is a greater than usual possibility of conflict with unalerted traffic, such as CTAF aerodromes.

Any safety output issued as a result of this analysis will be published in the Bureau's Quarterly Safety Deficiency Report.

Analysis

The pilot of the Chipmunk did not see the Metroliner. It is likely that the pilot commenced his take-off roll when the Metroliner was at least 3 NM from touchdown. At that distance, the Metroliner may not have been readily detectable by the Chipmunk pilot. His lookout for possible traffic would most likely have been directed towards the circuit and approach of runway 03 rather than towards runway 21 and he would not have been expecting to see traffic approaching from the opposite direction. With the aircraft in the level attitude during take-off, he would have been looking along the runway and his attention would have been focused on maintaining directional control. The Metroliner would most likely have been obscured from the Chipmunk pilot's view by the nose of his aircraft when he subsequently rotated to the climb attitude.

The crew of the Metroliner did not see the Chipmunk until that aircraft was almost overhead theirs. As they had not received any response to their broadcasts on the CTAF, they were relying on visual acquisition of any unalerted traffic as their only defence against a conflict. However, the Chipmunk was a small visual target with little relative movement. In addition, it had no anti-collision lighting and would initially have been below the Metroliner crew's horizon. The contrast between the background and the colour of the Chipmunk was minimal and would have made the aircraft difficult to discern.

The straight-in approach procedure at CTAF aerodromes did not appear to adequately address the limitations of unalerted "see and avoid" principles. The assumption of two pairs of eyes being more likely to detect unalerted aircraft than one pair of eyes, did not prove to be an adequate defence in this incident.

In this instance, the crew of the Metroliner elected to make a straight-in approach in wind conditions that most probably favoured a reciprocal runway direction. Without any response to their broadcast intentions, the crew probably assumed that there was no traffic and believed it was safe to use runway 21. As regulations in force at the time of the occurrence did not include a requirement for an airline operator to assess the circumstances and the likelihood of encountering non-radio traffic at individual locations, it was likely that many crews were conducting straight-in approaches as an expected routine. Had the crew been aware, for example, of the potential for greater numbers of recreational movements at weekends and on public holidays, they may have decided not to conduct the straight-in approach.

Although the company had provided a radiocommunication service to comply with the requirements for this procedure, its effectiveness to alert the crew to other aircraft was restricted by company procedures and by the physical location of the radio operator. The radio operator was not familiar with aircraft movements and had never been instructed to provide runway-in-use information. Had the radio operator been afforded a full view of the entire runway and the approach path of the Metroliner and permitted to issue traffic information, a timely warning may have been broadcast to the crew of the Metroliner about the presence of the Chipmunk.

The pilot of the Chipmunk chose to continue his flight without radio communication and without knowledge of a procedure that could place him in potential conflict with a passenger-carrying aircraft. Knowledge of scheduled aircraft movements at that location may have influenced the pilot to avoid commencing a non-radio flight when the arrival of a scheduled service was imminent.

Summary

Sequence of events

The crew of a Metroliner, conducting a scheduled passenger service from Sydney, reported that at 30 NM from Latrobe Valley, they obtained weather information from their ground agent on the common traffic advisory frequency (CTAF). They recorded the wind as light and variable. At approximately 17 NM, the co-pilot broadcast on the CTAF advising their intention to join for a 5 NM straight-in approach to runway 21. Two similar broadcasts were made, one at 10 NM and the other at 5 NM. At approximately 1 NM from touchdown, the crew saw a Chipmunk aircraft a short distance to their left and about 400 ft above them, travelling in the opposite direction. The crew continued their approach and landing as they considered that there was no further risk of collision.

The Chipmunk pilot was conducting a private flight. He reported that the aircraft radio had undergone maintenance prior to the incident flight and that he was unsure if a functional check of the radio had been made. He determined that the wind was a light north-easterly and elected to use runway 03. He broadcast on the CTAF that he was taxiing, and made a further transmission advising that he was backtracking along runway 03. He did not hear any response to either broadcast and had not heard the aerodrome frequency response unit. He assumed that his aircraft radio was not operating and proceeded with the flight without making any further radio broadcasts.

The pilot of the Chipmunk reported that he did not see any aircraft either when entering the runway or when lining up for takeoff. He departed and climbed away, unaware that the landing Metroliner had passed below him. Although he was aware that scheduled flights operated into the aerodrome, he was not familiar with those schedules. He was also unaware that such aircraft could conduct straight-in approaches to CTAF aerodromes. He reported that although his aircraft was equipped with a landing light, he was not in the habit of using it in daylight conditions.

Witness information

An instructor at the aerodrome reported that, at the time of the occurrence, the Chipmunk and the Metroliner were the only aircraft in the circuit. He added that other aircraft movements that day had been made from runway 03.

Following this incident, another instructor observed the straight-in approach procedure under similar conditions. He stationed himself at a position similar to that of the Chipmunk pilot at takeoff in order to determine the visibility of the approaching Metroliner. He reported that when the crew broadcast their 5 NM position, he was only able to see the aircraft after several seconds of looking. However, at an estimated 3 NM, with the landing gear extended and the taxi light illuminated, it was much easier to see the aircraft.

Weather

Weather conditions at the time of the occurrence were described as fine and clear with good visibility. Witnesses on the ground reported the wind as 5-8 kt from the north-east. Data recorded from the automatic weather station (AWS), indicated that a north-east wind had prevailed from 1100 Eastern Standard Time (EST) onwards. The Latrobe Valley METAR (meteorological observation) at 1304 EST indicated that the wind direction was 070 degrees magnetic and the windspeed was 7-10 kt. Those conditions favoured the use of runway 03.

Straight-in approach procedures

On 26 March 1997, the Civil Aviation Safety Authority permitted multi-crew regular public transport aircraft to conduct straight-in approaches to non-controlled aerodromes other than those within a mandatory broadcast zone. Effective from 1 May 1999, amendment 35 to the Civil Aviation Orders (CAO) part 82.3 incorporated a new sub-section 5A that required the provision of a ground-based radiocommunication service at aerodromes where straight-in approach procedures were conducted. However, following industry concerns about the operator's liability in relation to the provision of traffic information and the cost to airlines of providing such a service, that section was amended. CAO amendment 41 was issued with a new sub-section 5B that restricted the information to be given by the radiocommunication service to wind direction and runways in use at the aerodrome.

The company operating the Metroliner contracted the services of a ground-handling and booking agent to perform the required radiocommunication service, and personnel were trained and approved to provide that service. The procedure required the agent's staff to obtain weather information from the AWS and, when requested, broadcast this information to company pilots on the CTAF. Information about other traffic or the runway in use was not transmitted.

The agent advised that crews could obtain traffic and runway information from other aircraft on the CTAF. Other duties performed by the agent's staff precluded them from continuously monitoring the CTAF for information about other traffic. Additionally, the company radio was situated in the airport terminal and only a limited view of the airfield was afforded through the windows. Visual observation of aerodrome traffic from this location was not possible. The Chipmunk would not have been visible from this vantage point at any time it was taxiing or airborne.

There were no specific company instructions for crews making straight-in approaches at CTAF aerodromes. Company management personnel were satisfied that the procedures contained in the Aeronautical Information Publication were adequate. Company standard operating procedures required the landing and recognition lights to be turned on as aircraft were approaching 10,000 ft when transition checks were being completed. The taxi light was not to be turned on until after the landing gear was extended. The crew reported that that procedure had been followed.

The pilot in command advised that the crew's preferred choice of runway direction at Latrobe Valley on the flight from Sydney was runway 21. This not only reduced flying time but also allowed crews the 3-minute cooldown period for the engines while backtracking to the terminal. It also avoided running the engines near the terminal and creating unnecessary noise.

Determination of the runway in use, as required by the Aeronautical Information Publication (AIP) procedure, was assumed by crews to be either the reported runway being used by other traffic in the circuit or, in the absence of other traffic, runway 21, provided that wind conditions were favourable. The view expressed by the pilot in command was that the straight-in approach procedure offered a better level of safety than that provided by the normal circuit entry and that it was more expedient. He believed that the procedure resulted in less circuit manoeuvring and a reduced risk of traffic conflicts.

Aerodrome traffic

This incident occurred on a Sunday afternoon. The airline operated six services per week into Latrobe Valley but only one of these flights was conducted on a weekend. The pattern of activity at the aerodrome was not recorded however, staff at the Aero Club were able to confirm that most recreational flying activity took place at weekends and on public holidays. Only a small number of aircraft operating from the aerodrome were not radio-equipped. The scheduled movements at Latrobe Valley were not published in any of the aeronautical publications.

Occurrence summary

Investigation number 199903768
Occurrence date 25/07/1999
Location 2 km NNE Latrobe Valley, Aero.
State Victoria
Report release date 23/12/1999
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Separation issue
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer Fairchild Industries Inc
Model SA227
Registration VH-DMO
Serial number DC-870B
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Sydney, NSW
Destination Latrobe Valley, VIC
Damage Nil

Aircraft details

Manufacturer De Havilland Canada/De Havilland Aircraft of Canada
Model DHC-1
Registration VH-DHW
Serial number DHC 770
Sector Piston
Operation type Private
Departure point Latrobe Valley, VIC
Destination Yarram, VIC
Damage Nil

de Havilland Canada DHC-8-202, VH-SDA, 407 km north-west of Cairns Aerodrome, on 25 June 2009

Summary

While cruising at flight level 220 between Kimmi and Ablok, approximately 220 NM north-west of Cairns, the crew of the Dash 8 heard a muffled sound that was followed by an increase of the left engine inter turbine temperature. The crew reduced the engine power and returned the aircraft to Cairns.

The engine examination revealed that the reported problem was the result of a failure of the number 5 bearing. The bearing cage contained two cracks and was open. Some roller pockets in the bearing cage were enlarged and distorted, which allowed the rollers to rotate in the plane of the cage. Some other rollers were immobilised and contained large flats. Six of the 12 rollers had a smaller diameter than the rest. Their surface was abraded and smeared, consistent with heavy contact loads.

Because of several similar failures, the engine manufacturer had issued service bulletin number 21472R2, on 25 February 1999, introducing an improved number 5 bearing. The service bulletin advised that engines of serial numbers subsequent to the failed engine were already fitted with the new bearing. It further recommended that number 5 bearings on all other Pratt & Whitney PW100 engine models should be replaced when the engines were disassembled and access was available. The improved bearing had not been installed on this engine.

Occurrence summary

Investigation number 199903738
Occurrence date 25/06/1999
Location 407 km NW Cairns, Aero.
Report release date 15/11/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Abnormal engine indications
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer De Havilland Canada/De Havilland Aircraft of Canada
Model DHC-8
Registration VH-SDA
Serial number 482
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Cairns, QLD
Destination Horn Island, QLD
Damage Minor

Transponder related between a Boeing 747-438, VH-OJB and Tupolev KGA515, Lajak, on 17 July 1999

Summary

While maintaining flight level (FL) 330, the crew of a Boeing 747 (B747) aircraft monitored the position report from the crew of a Tupulov 154 (Tu154) aircraft. This position report indicated that the Tu154 was estimating position LAJAK at 1907 UTC. The B747 was estimating LAJAK at 1906. Both aircraft were maintaining FL 330.

The crew of the B747 advised air traffic control of the conflict, who directed the crew of the Tu154 to descend to FL 290. The aircraft were vertically separated at LAJAK.

Despite the close proximity of the aircraft, the B747's traffic alert and collision avoidance system (TCAS) did not display the TU154. The crew confirmed with air traffic control that the secondary surveillance radar (SSR) transponder mode C function of the Tu154 was operating correctly. The crew of the B747 reported that their aircraft's TCAS system was functioning correctly and that they were able to monitor aircraft at other stages of the flight.

Investigation revealed that some Eastern Bloc SSR transponders may be selected by the crew to output altitude information in either feet or metres. The investigation was unable to determine if the Tu154 was equipped with this type of transponder.

The operator of the B747 issued an alert to all crews regarding the capability of Eastern Bloc transponders to output altitude information in either feet or metres and if metres was selected the aircraft may not be visible on TCAS.

Occurrence summary

Investigation number 199903711
Occurrence date 17/07/1999
Location Lajak (Reporting Point)
State International
Report release date 06/10/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer The Boeing Company
Model 747
Registration VH-OJB
Serial number 24373
Sector Jet
Operation type Air Transport High Capacity
Departure point London, UK
Destination Bangkok, THAILAND
Damage Nil

Aircraft details

Manufacturer Tupolev
Model Tu-154
Registration KGA515
Sector Jet
Operation type Air Transport High Capacity
Damage Nil

British Aerospace Plc 3201, VH-XFC, 9 km north-north-east of Brisbane, on 28 July 1999

Safety Action

Local safety action

The Airservices Australia investigator made the following recommendations:

"The MORETON GROUP Leader to include the application of the "Sight & Follow" procedure as a specific subject in all future Refresher Training programs with case studies for analysis. (e.g. the practicality of sighting traffic same level eleven o'clock at ten miles in a period of high cockpit workload.)

Consideration given to include in MATS 4-5-1 para 10 specific reference to "---their number in the landing sequence ----" and not limit this reference to same page, para 15, second sentence under the title of Visual Separation by Aerodrome Controllers."

Australian Transport Safety Bureau safety action

As a result of this occurrence the Australian Transport Safety Bureau (formerly BASI) is currently investigating a safety deficiency. The deficiency relates to the training provided to Airservices Australia's approach controllers, in particular human factors awareness training on the limitations of human performance.

Significant Factors

  1. The approach controller used the "sight and follow procedure" in an inappropriate circumstance. That is, the controller transferred the responsibility for separation to the pilot in a situation where the positive application of a separation standard may have been more appropriate.
  2. The approach controller requested the crew of the Metroliner to sight the Jetstream in circumstances where a positive sighting may have been improbable.
  3. The crew of the Metroliner sighted and followed the BAe 146 rather than the Jetstream

Analysis

Notwithstanding the different profiles of the two aircraft, type identification of either aircraft would have been virtually impossible to determine at the ranges of the aircraft, that is beyond 6.8 NM. This is because contrast, which is the difference between the brightness of the aircraft against the brightness of the background, reduces with increasing range. Further, target identification would have been hampered by contour interaction. This phenomenon occurs where the outline of a target aircraft interacts with the contours present in the background. This is a particular problem at lower altitudes where aircraft appear against complex backgrounds.

When the crew of the Metroliner was instructed to report when they could see the other aircraft at 11 o'clock, the BAe 146 was the only aircraft discernible to them. With its side profile, the BAe 146 was at the extreme limit of visual acuity and could easily have been mistaken for a Jetstream, particularly as no other aircraft was in their field of vision. The Jetstream, with its head-on profile and greater range, would have been impossible to see at 9.8 NM. Moreover, because its actual position was not correctly described to the crew, they were looking for the Jetstream in the wrong place.

The approach controller may have realised that there was potential for mis-identification of the two aircraft. This is suggested by his action of cautioning the Metroliner crew about the BAe 146 that was on short final. However, the controller did not provide additional information that would have provided an assurance that the pilot was following the correct aircraft.

The identification of the potential conflict and action taken by the aerodrome controller was timely and appropriate. The vigilance and prompt action of the aerodrome controller acted as a safety defence to reduce the possibility of collision between the aircraft.

Summary

There were three aircraft in the approach sequence to land on runway 19 at Brisbane: a British Aerospace 146 (BAe 146), VH-JJS, on final at 2 NM; a British Aerospace Jetstream 3200 (Jetstream), VH-XFC, on right base at 6.5 NM with approximately 8 track-miles to touchdown; and a Fairchild SA226 Metroliner (Metroliner), VH-TFQ, on an oblique left base at 6.5 NM with approximately 10.5 track-miles to touchdown. Analysis of recorded voice data confirmed that the approach controller advised the crew of the Metroliner that they were number 3 in the sequence and that the Jetstream was number 2. Subsequent to that advice, the controller advised the Metroliner crew that the aircraft they were to follow was at 11 o'clock, 10 NM at 1600 ft. They were instructed to report when they could see that aircraft. The crew responded "Traffic sighted". The crew of the Metroliner was then assigned responsibility for separation from the Jetstream by being cleared to manoeuvre as required to make a visual approach and to "follow the Jetstream". In the same transmission, the crew were cautioned about the BAe 146 "on a very short final runway 19" and instructed to contact the tower.

When the crew transferred to the tower frequency, the aerodrome controller realised that the Metroliner was following the wrong aircraft, the BAe 146, and could be in conflict with the Jetstream. The controller instructed the Metroliner crew to orbit their aircraft on left base to increase its separation with the Jetstream. Analysis of recorded radar data indicated that separation between the Metroliner and the Jetstream had reduced to 1.2 NM when they were at the same level.

The crew of the Metroliner did not recall being cautioned about the 146. The aircraft they had sighted and followed was not the Jetstream but the BAe 146, which resulted in the breakdown of separation.

The Manual of Air Traffic Services (MATS) stated in MATS 4-5-1, paragraph 7:

"Correct identification of the aircraft from which separation must be maintained is essential".

Paragraph 10 stated:

"The traffic information provided shall contain as much as is necessary of the following to assist the pilot in identifying the other aircraft:

  1. type, and description if unfamiliar;
  2. level;
  3. position information either by clock reference, bearing and distance, relation to a geographical point, reported position and estimate, or position in circuit;
  4. intentions, or direction in flight."

Analysis of the radar data indicated that at the time the crew was asked to report sighting the aircraft, the BAe 146 was in the Metroliner's 11 o'clock relative position at 6.8 NM and displayed an oblique, side profile. The position of the Jetstream was more to the Metroliner's 12 o'clock relative position, at 9.8 NM and displayed a head-on profile.

Occurrence summary

Investigation number 199903602
Occurrence date 28/07/1999
Location 9 km NNE Brisbane, Aero
State Queensland
Report release date 12/05/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Loss of separation
Occurrence class Incident
Highest injury level None

Aircraft details

Manufacturer British Aerospace
Model 3200
Registration VH-XFC
Serial number 949
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Roma, QLD
Destination Brisbane, QLD
Damage Nil

Aircraft details

Manufacturer Fairchild Industries Inc
Model SA226
Registration VH-TFQ
Serial number TC-395
Sector Turboprop
Operation type Air Transport Low Capacity
Departure point Coolangatta, QLD
Destination Brisbane, QLD
Damage Nil

Aircraft details

Manufacturer British Aerospace
Model BAe 146
Registration VH-JJS
Serial number E2093
Sector Jet
Operation type Air Transport High Capacity
Departure point Unknown
Destination Brisbane, QLD
Damage Nil

Cessna 172H, VH-RLO, on 16 July 1999

Factual Information

The Cessna 172 was being used to assist a ground party of station hands to muster sheep on a station property approximately 46 km south-west of Onslow, WA. The manager of the station reported that the aircraft was being used to spot livestock on the ground and to muster sheep using a pilot-activated siren on the underside of the fuselage.

The aircraft was being flown along a generally east-west track, from one side of the paddock to the other, which gradually progressed towards the northern boundary. Although members of the ground party were unable to estimate the height at which the aircraft was operating, they did report that the aircraft siren was effective in moving the sheep. An experienced mustering pilot stated that a siren fitted to an aircraft would probably be quite ineffective at a height of 500 ft above ground level.

The station manager reported that the pilot appeared to be attempting to position the aircraft to cut off a mob of sheep that had broken away from the group he was following. He saw the aircraft pass approximately overhead and in a westerly direction before it commenced a left turn.

The manager looked away from the aircraft but reported that he could clearly hear its engine, which sounded normal. He immediately looked up when he heard the sound of an impact and saw that the aircraft had crashed approximately 100-200 m from where he was standing.

As a result of the accident the pilot sustained fatal injuries and the aircraft was destroyed. Damage to the aircraft was consistent with it having impacted the ground in a near vertical attitude at a low forward speed. A significant quantity of fuel was later recovered from the aircraft wreckage. There was no evidence that a mechanical defect had contributed to the accident.

The property owners had employed the pilot to fly their aircraft to assist with mustering operations. They stated that they had little knowledge of operating a light aircraft in support of their primary production activities. One of the owners was aware of a mustering type endorsement and reported that despite contacting a number of organisations and authorities, he had experienced difficulty in finding somebody to conduct mustering training for the pilot.

The pilot was issued with his private pilot licence (aeroplanes) on 4 June 1999, 6 weeks before the accident. At the time of the accident, the pilot had accumulated about 191 hours aeronautical experience, which included some helicopter training. No evidence was found to indicate that the pilot had received any formal low-flying training or that he was qualified to conduct mustering operations. Investigators were told the pilot had arranged to do training for a mustering endorsement once he had enough experience to be endorsed.

Flight and duty time limitations are specified for pilots engaged in commercial operations. However, as this mustering operation was being conducted in the private category, there was no requirement for the pilot or the aircraft operator to comply with these limitations. Consequently, the pilot was responsible for determining his daily flying activities. This was done in conjunction with the property owners, property manager and the mustering party. Investigators were told that the pilot typically commenced flying at approximately 0700 local time and continued through the day, until the last paddock had been completed.

During the course of the investigation the pilot's recent flight and duty times were reviewed to determine whether fatigue had been a factor leading to the occurrence. He had flown at least 68 hours in the 9 days since arriving at the station and had not taken a day off during this period. On the day of the accident, he had flown at least 8 hours 30 minutes. He was known to take short breaks from airborne operations about every 4 hours, during which time he would refuel the aircraft.

Analysis

On the day of the accident, the pilot had been flying the aircraft at low level for most of the day, with minimal rest periods. He had only recently qualified for his private pilot licence and a significant portion of his total flying hours had been accumulated in the 9 days before the accident. During this period, he had exceeded the flight and duty times normally permitted for a commercial operation.

Fatigue can diminish human performance, particularly with tasks requiring sustained attention and rapid reaction times. It may impair a pilot's ability to judge distance and speed, and it increases reaction times. It may also lead to poor decision making. Heat, noise and vibration may exacerbate these effects.

A human factors report noted that the pilot had worked long hours in a job in which he was inexperienced and that he probably found this type of flying both physically and mentally demanding. The report concluded that at the time of the accident the pilot was suffering from the effects of fatigue, possibly impairing his ability to safely operate the aircraft. The pilot was not qualified to conduct mustering or low flying operations. Without such qualifications, the pilot was legally required to operate no lower than 500 ft above ground level. At this height, the aircraft may have been of some use in spotting sheep but probably would have been ineffective at mustering.

The pilot had received minimal training to identify the visual illusions associated with low level flight. As such it was considered unlikely he was aware of appropriate techniques to safely manoeuvre the aircraft at low level. Several visual illusions affect pilots of low flying aircraft. An untrained pilot would be particularly susceptible to such illusions, some of which may prevent correct estimation of airspeed or making appropriate control inputs during a critical phase of flight.

The property owners had little aviation experience to help them manage the hazards of this type of operation. Although one of the owners knew that pilots needed special training for mustering, the accident pilot was employed while still unqualified.

Pilot fatigue, a lack of low flying training and no appropriate supervision of a relatively inexperienced pilot were identified as possible contributing factors to the accident. The immediate circumstances of the aircraft impacting the ground could not be established.

Summary

The Cessna 172 was being used to assist a ground party of station hands to muster sheep on a station property approximately 46 km south-west of Onslow, WA. As a result of the accident the pilot sustained fatal injuries and the aircraft was destroyed.

Occurrence summary

Investigation number 199903463
Occurrence date 16/07/1999
Location 46 km SW Onslow, Aero.
State Western Australia
Report release date 08/08/2000
Report status Final
Investigation type Occurrence Investigation
Investigation status Completed
Mode of transport Aviation
Aviation occurrence category Collision with terrain
Occurrence class Accident
Highest injury level Fatal

Aircraft details

Manufacturer Cessna Aircraft Company
Model 172
Registration VH-RLO
Serial number 17255432
Sector Piston
Operation type Private
Departure point Minderoo Station, WA
Destination Minderoo Station, WA
Damage Destroyed