

Fire on board the livestock carrier Ocean Drover, Fremantle, Western Australia, on 9 October 2014
Final report
Report release date: 11/03/2016
Safety summary
What happened
On the morning of 9 October 2014, a fire started in Ocean Drover’s crew accommodation while the livestock carrier was berthed in Fremantle, Western Australia. The fire quickly spread across both accommodation decks. The ship’s crew and shore emergency response teams responded and fire-fighting efforts continued for the rest of the day.
By the time the fire was extinguished late that evening, the ship’s accommodation areas and its navigation bridge had been extensively damaged. Four of the ship’s crew sustained injuries that required medical treatment.
What the ATSB found
The ATSB found that the fire started in a centrally located forward cabin on Ocean Drover’s upper deck. The intensity of the fire and the severity of the damage made it impossible to identify an exact point of origin or source of the fire.
The ATSB investigation found that the cabin door was left open after the fire was discovered allowing smoke and flame to spread beyond the cabin. Further, the bridge deck stairwell fire door was hooked open, which allowed the fire to rapidly spread and engulf both the upper and bridge decks.
The investigation also identified that the ship’s crew did not complete a muster and accurate head count when responding to the fire.
While cigarette smoking was not identified as a contributing factor, it was found that the smoking policy and associated risk controls on board were not effectively managed.
What's been done as a result
Ocean Drover underwent extensive post-fire repairs before it could return to service. During the repair period, the ship’s managers took pro-active safety action to avoid a similar incident in the future. All cabins in the ship’s accommodation were fitted with smoke detectors. The bridge deck stairwell fire door was replaced with one that is not fitted with a hold back arrangement (to comply with mandatory regulations). Notices posted on both sides of the door require it to be kept closed.
The ship’s managers have revised the shipboard smoking policy and restricted smoking to designated rooms, which exclude crew cabins. Designated smoking rooms are provided with safety ashtrays and sand bins, and warning signs have been posted in accommodation areas. The managers promulgated the lessons learned from the fire and safety action taken across the fleet through procedural changes and safety meetings.
Safety message
Containing a shipboard fire in the compartment where it originates is critical to firefighting. Effective containment relies on maintaining the integrity of fire divisions, including bulkheads, decks and doors. In this regard, particular attention must be paid to ensuring fire doors, designed to limit or prevent the spread of fire, are never latched/lashed open, or otherwise compromised.
The occurrence
At 0700[1] on 9 October 2014, Ocean Drover’s (Figure 1) crew started final preparations to load cattle in Fremantle, Western Australia. The first transport of livestock was expected to arrive on the wharf at 0800 and the boatswain (bosun) and 21 ordinary seamen (OS) were preparing the livestock pens.
Figure 1: Ocean Drover

Source: Australian Transport Safety Bureau (ATSB)
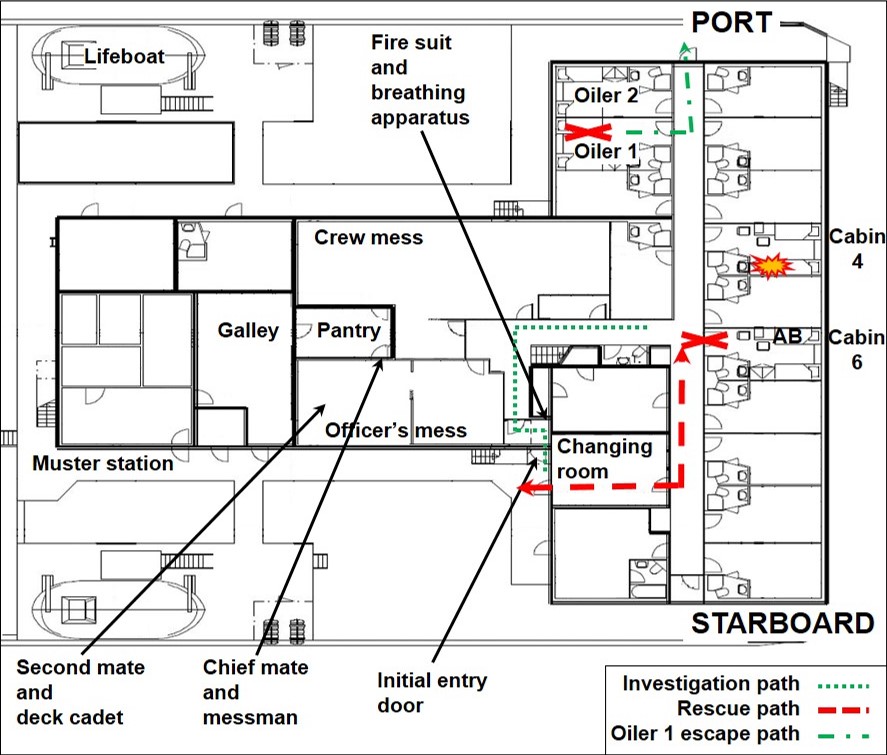
At the time, most other crewmembers, including watch keepers, were in the accommodation spaces. One able seaman (AB) and an oiler (oiler 1) were asleep in their cabins after their night watches (Figure 2). Another crewmember, oiler 2, was due to start work in the engine room at 0800 and was in an adjoining cabin.
Detection of the fire
Shortly after 0745, when oiler 2 left his cabin, he immediately smelled smoke and heard a crackling sound. He traced the sound to the nearby cabin 4. He opened the door and was confronted by flames, intense heat and thick, black smoke. He dropped to his hands and knees and hurried away toward the officer’s mess room to raise the alarm. The door of cabin 4 remained open.
At about 0750, oiler 2 entered the officer’s mess room (Figure 2) shouting that there was a fire. The chief mate, second mate, deck cadet (cadet) and mess man were in the mess room. At about the same time, the ship’s fire alarms began to sound.
The chief mate, second mate and cadet went forward along the corridor to investigate. However, they had to retreat because of the dense smoke. They exited the accommodation onto the open deck on the starboard side. The second mate and cadet collected the self-contained breathing apparatus (BA) and firefighter’s outfit from the nearby fire locker in preparation to fight the fire.
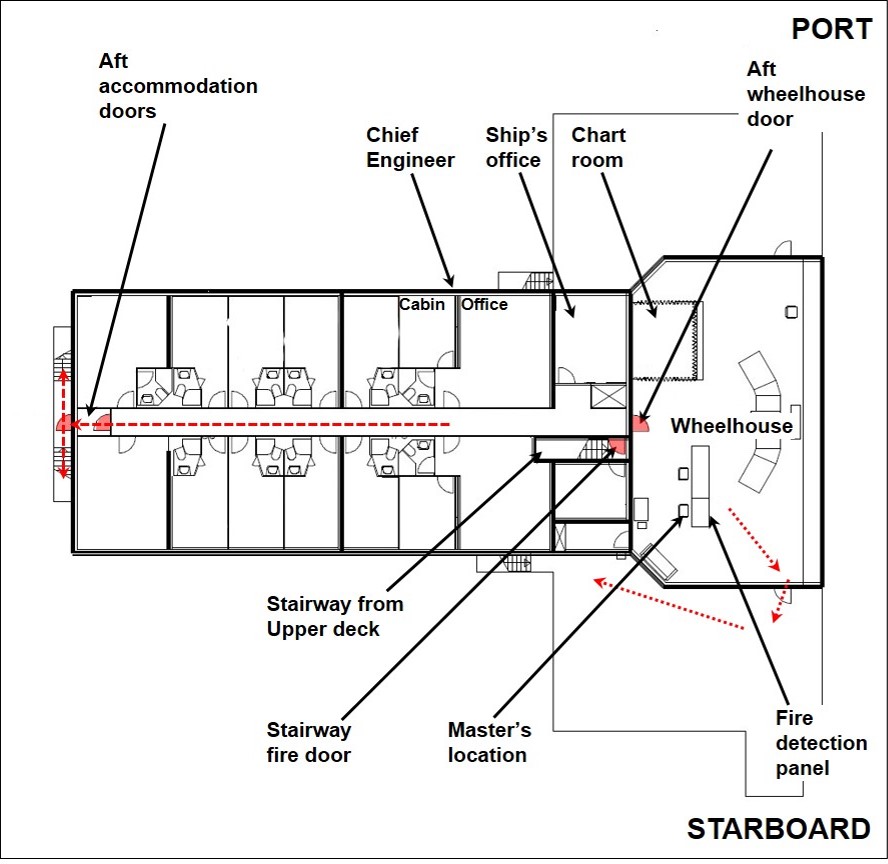
At 0750, Ocean Drover’s master was in the navigation bridge (wheelhouse) on the bridge deck (Figure 3) when the fire detection system alerted him to a fire in the accommodation.[2] Shortly thereafter, the ship’s fire alarms began to sound. When the master opened the aft wheelhouse door, he saw smoke coming up the nearby stairwell from the deck below.
Figure 2: Diagram of upper deck accommodation showing key locations and paths
Source: Wellard Ships with annotations by ATSB
The master retreated into the wheelhouse and called the chief engineer. He asked the chief engineer to go to the engine room and prepare the fire pump. The master then left the wheelhouse through the starboard bridge wing doorway and went down to the upper deck where he met the chief mate. They agreed that the second mate, who had already started donning the firefighter’s outfit, should attempt to enter the accommodation to investigate.
The chief engineer was in his office on the bridge deck, when alerted to the fire. He heard voices, smelled something burning, and went to investigate. He went forward along the passageway but was unable to go down the stairs due to thick smoke coming up from the deck below.
He returned to his cabin and dressed in work clothes. By the time he left his cabin, the smoke was thick and low in the passageway. He met the second engineer and told him to go to the fan room and shut down the accommodation ventilation fans. They exited the bridge deck via the aft doors and stairs.
Shipboard response
The sounding of the fire alarm throughout Ocean Drover alerted the crew working in the livestock pens. They began moving to the ship’s upper deck, above the livestock pens, and forward toward the accommodation and muster stations. Thick black smoke was now coming from the accommodation and the crew began to assemble in teams as practised during fire drills. Two crewmembers collected the second firefighter’s outfit and BA stowed in the deckhouse midway along the upper deck, and brought it forward with them.
Figure 3: Bridge deck plan
Source: Wellard Ships with annotations by ATSB
The chief mate and the bosun met on the starboard side of the accommodation. After some discussion, the bosun directed the assembled teams to close ventilators and prepare fire hoses to boundary cool the accommodation superstructure.
By this time, the chief engineer had exited the bridge deck and the second engineer had gone to the fan room and stopped the ventilation fans. Once on the upper deck, the chief engineer saw the chief mate and second mate busy with the firefighter’s outfit and BA. He then went around the deck toward the port side, where he met the ship’s electricians. He checked that the emergency fire pump had been started and that electrical power to the accommodation areas was being isolated.
At about 0800, the second mate, wearing a firefighter’s outfit and BA, entered the accommodation via the starboard upper deck doorway, adjacent to the external stairs up to the bridge deck (green dotted path in Figure 2). Once inside, he moved along the passageway, inboard and then forward, toward the crew cabins.
At about this time, the AB sleeping in cabin 6 was woken by the fire alarm. He could not see or smell any smoke and opened the cabin door to investigate. He was engulfed by heat and smoke and retreated into the cabin. A short time later, shouting for help, he exited the cabin to escape but was overcome by smoke and collapsed in the cabin’s doorway.
Meanwhile, the second mate moved forward along the fore-aft passageway. He heard the AB’s calls for help but was unable to reach him because of the heat and smoke. Retracing his steps, he returned to the starboard deck to reconsider rescue options.
Shortly afterwards, the second mate re-entered the accommodation through the changing room which led directly to the port-starboard corridor (red dashed path in Figure 2). The chief mate stood by outside the changing room and handled the safety line attached to the second mate. With a fire extinguisher in hand, the second mate crouched low and entered the corridor. The smoke was very thick, he could not see and could no longer hear any calls for help. He dropped to a crawling position and began feeling his way further along the corridor.
When the second mate had crawled a few metres, he felt a body lying in one of the forward doorways (the collapsed AB). He manhandled the non-responsive man out of the doorway and back along the corridor from where he had come and into the changing room. With the chief mate’s assistance, the AB was taken through the changing room and out onto the open deck. The AB remained non-responsive so the second mate placed his BA mask over the AB’s face. Moments later, the AB coughed and began breathing. He was then moved clear of the smoke and firefighting effort.
Meanwhile, oiler 1 had not been woken by the fire alarms. However, he awoke coughing, in his smoke-filled cabin. When he tried to leave his cabin, he found the door handle hot and the corridor filled with thick black smoke. He retreated into his cabin but after some thought, decided to leave. He moved to the nearest exit door on the port side and made good his escape. Outside, he was assisted by crew there preparing fire hoses.
Shore emergency response
On the wharf, shore workers preparing for loading livestock had heard Ocean Drover’s fire alarms. They also saw smoke coming from the ship’s accommodation. Multiple telephone calls, from several sources, were made to the emergency triple zero (000) telephone service requesting fire brigade and ambulance assistance at the wharf.
At 0756, the Western Australia Department of Fire and Emergency Services (DFES) received the first of several calls reporting the fire. Multiple DFES fire appliances were dispatched.
By about 0800, the chief mate was directing the firefighting efforts of the ship’s crew. The master returned to the wheelhouse, telephoned the agent and requested immediate assistance to fight the fire. Shortly afterwards, he returned to the upper deck and instructed the third mate to account for the crew. The third mate took a crew list from the starboard lifeboat to carry out the task.
At 0802, the St John Ambulance state operations centre received a call requesting medical assistance at the wharf. Several ambulances were dispatched. By then, the injured AB had been assisted onto the wharf by other crewmembers in preparation for medical assistance.
At 0811, the first DFES fire appliance arrived on the wharf. The DFES Incident Controller (IC) directed a fire team to board Ocean Drover and assess the situation.
By 0825, further fire appliances, including four harbour tugs, had arrived on the scene. These units started applying water to the outside of the ship and its accommodation block.
At about 0840, the IC instructed Ocean Drover‘s crew to move aft and well clear of the accommodation. The crew assembled near the funnel, where the third mate completed accounting for the crew. The master was satisfied that no one was missing and, at 0850, he notified the IC that all crewmembers were accounted for.
The firefighting continued for the rest of the day. More than 50 fire appliances and over 100 fire fighters and shore personnel were involved. All of the ship’s crew were medically assessed on the wharf and four were taken to Fremantle Hospital. Of these, the injured AB was admitted to the hospital while the others were treated and released.
At about 2245, DFES reported that the fire had been extinguished. Thereafter, fire crews carried out regular rounds of the ship’s accommodation, recording temperatures and checking for signs of flare-up.
At 0930 on 10 October, DFES handed control of the ship to Fremantle Ports. The ship’s wheelhouse and accommodation areas were extensively damaged—the fire had gutted the wheelhouse, the wheelhouse top air handling room and the majority of crew cabins and spaces.
During November 2014, Ocean Drover was towed to a shipyard in Singapore for extensive repairs to the navigation bridge (wheelhouse) and accommodation areas. The ship left the shipyard and returned to service on 18 March 2015.
Figure 4: Wharf CCTV footage at about 0800 clearly shows flames in cabin 4

Source: Western Australia Department of Fire and Emergency Services (DFES)
__________
- All times referred to in this report are local time (WST), Coordinated Universal Time (UTC) + 8 hours.
- The audio-visual alarm on the panel is designed to go into alarm for a short time before sounding the fire alarms throughout the ship.
Context
Ocean Drover
At the time of the fire, Ocean Drover was the world’s largest, purpose-built livestock carrier with an overall length of 176.60 m and a capacity of 75,000 sheep or 18,000 cattle. The ship was built in 2002 at Uljanik Brodogradiliste shipyard, Croatia. At the time of the fire, it was registered in Singapore and classed with Registro Italiano Navale (RINA). The ship was owned by Wellard Estates, Australia, managed by Wellard Ships, Singapore, and operated by Korkyra Shipping, Croatia.
Crew
At the time of the fire, Ocean Drover had a crew of 50. The master and 12 officers were Croatian or Indian, while most of the ratings were Filipinos. The 21 ordinary seamen on board were employed mostly for handling livestock. Three technicians were also on board for the voyage.
The master and officers were accommodated in the bridge deck cabins. The upper deck accommodated 34 crewmembers in 12 multiple berth cabins and two, single berth cabins. The three technicians were in the Suez Canal crew cabin, on the aft, port side of the upper deck.
The master held a Croatian master’s certificate of competency and had 36 years of seagoing experience. He had been on board Ocean Drover, his first livestock carrier, for about 6 weeks.
The chief mate held a Croatian chief mate’s certificate of competency and had 22 years of seagoing experience. Ocean Drover was his first livestock carrier and he had been on board for about 3 months.
The second mate went to sea in 2010 after completing his nautical training. He held a Croatian second mate’s certificate of competency. He joined Ocean Drover, his first livestock carrier, about 3 months before the fire for his first assignment as second mate. He had been a volunteer fire fighter in Croatia before going to sea.
The able seaman (AB) in cabin 6 had 8 years of seagoing experience. He had been on board Ocean Drover, his first livestock carrier, for about 6 weeks.
Oiler 1 had 10 years of seagoing experience. Ocean Drover was his first livestock carrier and he had been on board for about 3 months.
All of the ship’s crewmembers had completed a basic firefighting course (as a minimum) as part of their training requirements for working on ships.[3]
Emergency muster and preparations
Emergency muster lists and instruction sheets were displayed at a number of locations on board Ocean Drover. Each crewmember was assigned to emergency response teams, and had a role based upon the type of emergency. Depending upon the team to which a crewmember was assigned, the three emergency muster locations were the:
- wheelhouse
- engine control room
- upper deck adjacent to the starboard lifeboat.
In the event of a fire on deck, the muster stations and roles/responsibilities of the emergency response teams were:
- Bridge team: Wheelhouse - command and control
- Attack team: Upper deck (starboard) – firefighting
- Support team: Upper deck (starboard) – support attack team
- Cooling team: Upper deck (starboard) – boundary cooling and support
- Engine team: Engine Control Room – technical support
- First Aid team: Upper deck (starboard) – medical support.
Any additional crewmembers were to muster at the upper deck station and follow instructions from the master or chief mate. Supernumeraries or passengers were to report to the wheelhouse.
Posted with the muster lists was an additional information document. This provided general emergency response advice not provided on the muster list itself. The firefighting section of this document included the following instructions:
- all personnel shall assemble in teams at their designated assembly areas
- team leaders shall communicate the head count to the master or duty officer
- at least two persons must enter any compartment with firefighter’s outfit and a charged fire hose.
Korkyra Shipping also maintained a contingency plan for its fleet. This plan provided guidance and advice to the master and company personnel for dealing with accidents and emergencies. It contained descriptions of preparations for the ship that may be of importance for actions and decisions to be made in different situations. Roles and responsibilities were defined and the plan included sections on fire emergency, reporting and drills. Fire drills were to be conducted on a monthly basis.
Fire protection arrangements
Thermal and structural boundaries divided Ocean Drover’s various spaces (areas) into vertical and horizontal zones. These spaces were classified in accordance with SOLAS,[4] based on fire risk.[5] Consequently, fire integrity standards applied to the boundaries, which formed the divisions between the adjacent spaces. The space classification determines the materials used to construct the solid divisions and openings therein.
The objectives[6] of the fire boundaries were to:
- prevent the occurrence of fire and explosion
- reduce the risk to life caused by fire
- reduce the risk of damage caused by fire to the ship, its cargo and the environment
- contain, control and suppress fire and explosion in the compartment of origin
- provide adequate and readily accessible means of escape for passengers and crewmembers.
Ocean Drover was constructed to regulation and fitted with the prescribed fire detection and protection requirements. Fire detection equipment was fitted in all accommodation common or general usage areas, with smoke detection in all corridors, stairways and escape routes.
The ship had two fire lockers – each fitted with a firefighter’s outfit and self-contained breathing apparatus (BA) with spare air bottles. One fire locker was located in the starboard access to the upper deck accommodation and the other in the deckhouse for the stairwell to the lower decks and starboard gangway (about 75 m aft of the first).[7]
Structural subdivision
Ship divisions are constructed to provide a minimum, verified level of protection in case of a fire. The divisions are classed based upon compliance with criteria set out in the regulations.
‘A’ class divisions are designed to prevent the passage of smoke and flame to the end of the one-hour standard fire test.[8]
‘B’ class divisions are designed to prevent the passage of flame only for the first 30 minutes of the fire test.
Both of these classes of divisions are also to prevent an average temperature rise on the unexposed face of more than 140 °C for the time listed in the item’s designation. For example, an A-15 class division will prevent the passage of fire and smoke for 60 minutes and limit the non-exposed surface temperature rise to less than 140 °C for 15 minutes.
‘C’ class divisions are constructed of approved non-combustible materials. These divisions do not need to meet the requirements for the passage of smoke and flame or temperature rise.
Ocean Drover’s crew cabins were segregated by ‘C’ class bulkheads and ceilings. That is, the divisions between cabins were not designed, or required, to limit the passage of smoke or flame, or limit temperature rise across them. Cabin bulkheads bordering passageways were B-0 rated.
Stairways
Any stairway which penetrates only a single deck is required to be protected, at one level, by at least B-0 class divisions and self-closing doors. The regulations expressly state that self-closing doors shall not be fitted with holdback hooks.[9]
Ocean Drover had two accommodation decks joined by one internal stair with a self-closing door at the top.
Port of Fremantle
The Port of Fremantle is a State Government owned port, managed by the Fremantle Port Authority (Fremantle Ports). The port is situated at the mouth of the Swan River and is the principal commercial port for Western Australia. It comprises the inner harbour, within the estuary of the Swan River, and an outer harbour.
In the 2013-2014 fiscal year, 65 livestock ships called at Fremantle. About 141,000 cattle and 1,700,000 sheep were exported through the port.
Western Australia fire and emergency response arrangements
In Western Australia, the role of various agencies in emergencies is described in the West Australian State Emergency Management Plans (WestPlan). These include plans for hazardous material (HAZMAT) and Marine Transport Emergency (MTE)[10] incidents.
The management of an MTE involves multiple agencies with overlapping responsibilities. These agencies include the Department of Transport Western Australia (DoT), the Port Authority, the private companies operating ports (Marine Export Facility owner), the Department of Fire and Emergency Services (DFES) and the ship’s master. A unified command structure[11] is used to control the incident.
The DoT is the Hazard Management Agency[12] (HMA) for all emergencies involving a ship, including any MTE that occurs in all waters within the state. The Port Authority or Marine Export Facility company will perform the immediate response for an MTE within port boundaries. These organisations are to provide the Incident Controller[13] (IC) and act as the Controlling Agency.[14]
For incidents involving fire and any rescue, the DFES will assume the role of Hazard Management Agency. DFES will then provide the IC who has responsibility for the development of incident objectives and the management of response activities to achieve those objectives.
Fremantle Ports is identified as a support agency for the management of emergencies.
Port Marine Safety Plans
All port authorities and private companies operating ports in Western Australia are required to prepare, maintain and implement a Marine Safety Plan. These plans identify arrangements for managing MTE situations within port waters.
Fremantle Ports has an Incident Management Plan in place to satisfy this requirement.
Department of Fire and Emergency Services (DFES)
The DFES determines the response to an MTE based upon the location of the incident and the capabilities of the first arriving brigade. The DFES Marine Fire Emergency Response Guide (MFERG) provides the IC with guidance for establishing firefighting strategies and for recording incident information. Before committing any resources to firefighting or other duties, the IC is to conduct a dynamic risk assessment and decide on an attack strategy.
When DFES attends a shipboard fire, it is likely that the fire has progressed beyond the normal capabilities of the crew. Therefore, DFES firefighters are trained in specific areas of fighting marine fires. The DFES Marine Firefighting Training manual outlines fire training and skills provided to the firefighters, which are specific to fires on board ships.
__________
- STCW Code - Seafarer’s Training, Certification and Watchkeeping Code, 1995, as amended, Part A, Chapter VI, Section 1, Mandatory minimum requirements for familiarization and basic safety training and instruction for all seafarers.
- The International Convention for the Safety of Life at Sea, 1974, as amended.
- SOLAS Chapter II-2, Regulation 9 Containment of fire
- SOLAS Chapter II-2, Regulation 2 Fire safety objectives and functional requirements
- SOLAS Chapter II-2, Regulation 10.10.3.1 states: The fire-fighter's outfits…shall be kept ready for use in an easily accessible location that is permanently and clearly marked and, where more than one fire-fighter's outfit…is carried, they shall be stored in widely separated positions.
- A standard fire test is a test in which specimens of the relevant bulkheads or decks are exposed in a test furnace to temperatures corresponding approximately to the standard time-temperature curve in accordance with the test method specified in the Fire Test Procedures Code.
- SOLAS Chapter II-2, Regulation 9.4.2 Doors in fire-resisting divisions in cargo ships. At the time of construction (2002), SOLAS Chapter II-2, Regulation 47 Doors in fire resisting divisions applied. Both prohibit the use of holdback hooks.
- Marine Transport Emergencies, whatever their cause, may threaten or endanger life, property and/or the marine environment and require the coordination of a number of significant emergency management activities.
- Unified Command is a supporting principle to the Australasian Inter-service Incident Management System (AIIMS), which requires the inclusion of key decision makers from all combat agencies. The location of the vessel will determine which jurisdiction has responsibility for it, and what emergency response is appropriate.
- An agency designated to lead the response to emergencies in relation to the type of hazard for which it is prescribed.
- The incident controller is the person who has the overall control of the incident scene.
- An agency nominated to control the response activities to a specified type of emergency.
Safety analysis
The fire
On the morning of 9 October 2014, a fire started in Ocean Drover’s crew accommodation and quickly spread across two decks. Emergency response teams fought to control the fire for the rest of the day. Four of the ship’s crew sustained injuries requiring medical treatment. One of the four was hospitalised for smoke inhalation and burns.
The fire was extinguished late that evening. The ship’s wheelhouse and the accommodation areas were extensively damaged.
Area of origin
Investigations
The fire was investigated by the WA Police arson squad, DFES, ATSB and Burgoynes, a consulting company acting for the ship’s managers.
The fire burned for several hours at temperatures that exceeded 1,100 °C. As a result of the intensity of the fire and the severity of the damage, an exact point of origin or source of the fire could not be identified. However, the evidence, including witness statements, indicates that the fire originated in cabin 4 (Figure 5). The arson squad did not find any evidence of suspicious activity.
Figure 5: Interior of cabin 4 when first accessed after the fire

Source: DFES with annotations by ATSB
The DFES Fire Investigation and Analysis Unit investigation identified the following possible ignition sources in cabin 4:
- multiple electrical circuits
- electrical power outlets
- light fittings
- portable electrical fan
- mobile phone chargers
- unextinguished cigarette.
The findings of the investigations (including the ATSB’s) were consistent with respect to the possible ignition sources and the point of origin of the fire.
Electrical equipment
A large amount of electrical equipment was present in the accommodation space and cabins that could have provided the ignition source for a fire.
The construction of the accommodation space and crew cabins included fixed electrical equipment and wiring for hotel and other services as well as distribution pathways for other shipboard services.
In addition, Ocean Drover’s crew, like those of any other ship, took portable electrical items on board for personal use. The ship’s accommodation included several multi-berth cabins with as many as four occupants but as few as four electrical power outlets. This led to the connection of multiple devices to a single power outlet using equipment such as adaptor plugs.
No evidence was found to show that the fire started from an electrical fault or appliance. None of the crewmembers interviewed indicated that they had experienced any problems with the ship’s electrical systems.
Smoking
Smoking is a recognised fire hazard on board ships, and therefore is a controlled activity.[15] The amount of control placed on smoking depends upon things such as the ship type, its cargo and the port. Controls may include:
- allowing smoking only in authorised areas such as designated smoking rooms
- banning smoking in cabins and other areas
- restriction on the smoking-related materials which may be used, such as self-extinguishing ashtrays and matches or lighters
- clear advisory notices and signage regarding smoking
- complete prohibition of smoking.
Smoking was permitted on board Ocean Drover, and a number of crewmembers stated that smokers were encouraged to smoke in the common rooms (mess room) instead of cabins. However, they also stated that smoking did occur in cabins if all its occupants agreed.
Self-extinguishing safety ashtrays were provided for use. However, evidence was found that unapproved items, such as plastic water bottles used as makeshift ashtrays, were also used in cabins. This indicates that the smoking policy and associated risk controls on board Ocean Drover were not effectively managed.
While both occupants of cabin 4 smoked in the cabin, they had been on duty in the galley since about 0430 on the morning of the fire. The second cook returned to the cabin at about 0725 for a break but stated that he did not have a cigarette at that time.
Fire growth
Fuel load
The intensity of a fire will depend, in part, upon the amount of fuel available to burn. The fuel load will also affect the speed at which a fire will grow and spread. To limit the potential for fire growth, the types and quantities of the materials used in a cargo ship’s accommodation are regulated. There is no restriction, however, on the quality (or quantity) of the furniture, bedding and furnishings used to fit out cabins, offices or public spaces. As the number of personnel on board increases, the amount of such material will also increase. In addition, each person will bring personal and work items, such as clothing, on board with them. Therefore, the more personnel on board, the more potential fuel that is available to feed a fire.
Furthermore, Ocean Drover had multi-berth cabins. Such cabins increased the density of the combustible materials within the accommodation space. Therefore, once the fire began, there was a significant amount of closely stowed, combustible material available to burn.
Figure 6: A two-berth cabin after the fire (note fuel load and possible ignition sources)

Source: DFES
Fire spread
The fire was discovered after it was well alight and had been burning for some time. The cabin door then remained open as the crewmember hurried away to raise the alarm. The open door allowed the smoke and fire to spread to other areas of the accommodation, and to trigger the fire detection system.
Further, parts of cabin 4’s ceiling mounted ventilation system ducting melted allowing the fire into the space between the cabin ceiling and the deck above. The fire was then able to spread across the top and down into adjacent cabins and passageways. This pattern of top-down burn damage was found throughout both decks.
Ocean Drover’s internal accommodation stairwell had a self-closing fire door at the top – leading to the bridge deck. However, at the time of the fire, this stairwell fire door was held open by a hook and eye securing arrangement, contrary to regulations. The open door allowed the fire to spread to the bridge deck.
Further, when crewmembers from the bridge deck cabins responded to the emergency and proceeded out onto the open deck, the aft accommodation doors were opened and not subsequently closed (Figure 7). The external door was closed only after the fire was well established and ship’s fire parties were fighting the fire.
The open cabin door allowed the fire to spread out into the deck corridors. The open bridge deck doors then provided a path for the smoke and flame to quickly spread from the upper deck to the bridge deck.
Significantly, evidence of flashover found in many cabins indicated that temperatures were sufficiently high for all cabin contents to spontaneously ignite. The divisions separating Ocean Drover’s crew cabins were not designed to limit the passage of smoke or flame, or limit temperature rise across them. Therefore, the fire breached cabin walls and ceilings even though the cabin doors remained shut. It is likely, therefore, that the fire would have spread to other cabins even with cabin 4’s door closed.
A fundamental firefighting technique is to ensure a fire is confined within its compartment of origin by closing all compartment openings such as doors and windows. On Ocean Drover, the fire would not have spread as easily as it did, and the damage would not have been as severe as it was, if the cabin door and the bridge deck fire doors had been closed.
Figure 7: Bridge deck aft (note the damage near the door, which was initially open)

Source: DFES with annotations by ATSB
Navigation bridge (wheelhouse)
The wheelhouse of a ship is a vital communication and control area. As such, all round A-60 class boundaries protect it. During the fire, several cabins beneath the wheelhouse were severely damaged. This caused some areas of the deck of the wheelhouse to be charred and warped. The fire also consumed the ship’s office and the corridor immediately aft of the wheelhouse.
That is, all the wheelhouse boundaries that bordered other internal spaces were exposed directly to the fire. CCTV footage shows the wheelhouse was completely filled with smoke about 30 minutes after the fire began. Despite this, the DFES reported that the wheelhouse was not damaged by fire more than 3 hours after the fire was discovered. Shortly after, the wheelhouse caught fire and was severely damaged (Figure 8).
No evidence was found to suggest that the fire breached the wheelhouse deck or aft bulkhead. The DFES investigation found that the most severe damage was in the area adjoining the ship’s office. Firefighters also observed that the wheelhouse was at the point of imminent flashover at about 1200. It is likely, therefore, that a combination of the intensity and duration of the fire exceeded the fire rating of the wheelhouse boundaries. This led to ignition of combustible materials and the destruction of the wheelhouse.
Figure 8: Burnt out wheelhouse viewed from the port bridge wing (chartroom is aft)

Source: ATSB
Ship response
On 9 October, as the ship’s crewmembers moved forward along the upper deck, it was apparent to them that there was a fire in the accommodation and that some crewmembers were preparing to enter it. At this time, two crewmembers remained in their cabins, close to the fire. This information was, however, not known to the gathering crewmembers. Then, in the urgency to respond, a formal muster was not immediately completed and a head count was not taken.
A short time later, the third mate was directed by the master to check that all crewmembers were accounted for using a crew list. However, he was unable to account for all crewmembers at that time. It was not until about 90 minutes after the fire began, when the crew had evacuated aft, that all had been positively accounted for.
One of the aims of emergency and fire response procedures is the preservation of life. Fundamental to achieving this is knowing if people are missing. This requires having accurate details on the personnel expected to be on board and then accounting for them all as early as possible. The crew of Ocean Drover had these details, however, a muster and accurate head count were not completed until well after the incident began.
It was not possible, therefore, to ensure that all crewmembers were safely out of the accommodation. Fortunately, the number of crewmembers trapped in their cabins was low. One of those trapped was able to draw attention to himself and the other was able to make his own escape.
Rescue
During his first entry into the accommodation, the second mate heard the AB’s calls for help. He then acted selflessly, with quick thinking and courage in making a second entry and saving his shipmate. He was dressed in a firefighter’s outfit, safety line and breathing apparatus and took a fire extinguisher with him. The chief mate stood by outside the accommodation to provide support.
However, on both occasions that he entered the smoke filled accommodation, the second mate did so on his own. In doing this, accepted fire and rescue techniques and shipboard emergency procedures that warn against single person entries into a smoke filled space, were not followed. Those actions could have compromised the second mate’s safety but fortunately did not.
Effectiveness of crew emergency response
When the ship’s crew went to the accommodation, they found the chief mate and second mate occupied with preparing an entry into the accommodation. Therefore, the practised command structure for the fire response parties was disrupted.
Despite this, the ship’s crew, with limited guidance from the master and ship’s officers, organised themselves into cooling and attack parties prior to the arrival of the DFES (Figure 9).
As the emergency unfolded, the ship’s crew responded effectively. They followed their training and compensated for changes of leadership and personnel.
Figure 9: Ship's crewmembers fighting the fire with water hoses

Source: ABC News (www.abc.net.au/news)
Shore response
The first of many calls were received by the triple zero (000) national emergency telephone service at 0756, 6 minutes after the ship’s fire detection system was activated. Fremantle Ports were notified at about the same time and also called 000 and requested DFES assistance. Fremantle harbour assets, including the port emergency response vessel, were mobilised to assist. The first of several boats arrived at the ship at about 0800.
Several DFES fire appliances were dispatched and the first arrived on the wharf at 0811. At this time, the ship’s crew were conducting external firefighting efforts and preparing for possible attack team entry into the upper deck. The fire was well established on both decks of the accommodation and an initial DFES entry crew were sent on board to evaluate the situation. They reported fire temperature readings around 700°C and decided that entry was not to be made at this time.
On the wharf, DFES incident control management arrangements and firefighting plans had been made. Once the safety of all ship’s crewmembers was confirmed, the DFES response became a defensive one, containing and limiting the spread of the fire, rather than one of attack and extinguishing.
As the fire developed, and the opportunity arose, more offensive firefighting tactics were employed. These tactics included accommodation entries and use of high expansion foam to cool and extinguish. The fire continued to burn for several hours until brought under control at 1855. The DFES fire teams then continued to monitor the situation throughout the night.
The shore emergency services’ response was timely and with sufficient resources for the situation. However, they found that the thermal and structural boundary construction of the ship hampered their efforts to gain access and extinguish the fire in its early stages. The large compartments and the use of different classes of sub-division were unfamiliar to the firefighters.
DFES analysis of the fire and their response found that the construction of the ship helped the fire to spread. It did not allow firefighters to use their training, based on isolating and boundary cooling each compartment, to the best effect. However, the firefighting efforts were successful in confining the damage to the accommodation block.
Crew welfare
During the emergency, all crewmembers were medically assessed by paramedics. Four were taken to hospital of which one remained in hospital for 8 days being treated for smoke inhalation and minor burns.
While the number and severity of injuries was low, all crewmembers’ documentation, clothing and personal effects were damaged or lost in the fire. As such, a combined effort was launched to assist the welfare of the men. The local Flying Angel Club and Stella Maris Seafarers’ Centre provided counselling, clothing, meals, communication facilities and other amenities to the seafarers. The majority of crewmembers were accommodated at the Flying Angel Club.
Korkyra Shipping and Wellard Estates also provided emergency money and telephones for contacting families and arranged liaison with the relevant national representatives for all crewmembers. Local Filipino, Croatian and Indian communities were contacted and provided support.
In the days following the fire and investigation, the majority of crewmembers were repatriated. A small number of personnel stayed with the ship to assist with recovery activities.
__________
- The dangers of smoking, and its controls, are referred to in many marine regulations, codes, circulars and guidelines including SOLAS, the International Maritime Dangerous Goods (IMDG) Code, the International Safety Guide for Oil Tanker and Terminals (ISGOTT) and various codes of safe working practices for merchant seamen.
Findings
From the evidence available, the following findings are made with respect to the fire on board Ocean Drover while berthed in the Port of Fremantle on 9 October 2014. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
- At about 0750 on 9 October 2014, a fire started in crew cabin 4 located on the upper deck of Ocean Drover’s accommodation block. The fire’s exact origin or cause could not be identified due to fire damage. However, investigations found electrical sources or smoking-related activities were likely causes.
- Not closing the cabin door after the fire was discovered assisted the fire to spread beyond the cabin confines.
- The cabin’s walls and ceiling construction were not rated (nor required) to contain flame or smoke.
- Ocean Drover’s bridge deck stairwell fire door was fitted with a holdback hook in contravention of international regulations. The door was hooked open, which allowed the fire to spread to the bridge deck from the deck below. [Safety issue]
- Open fire doors at the aft end of the bridge deck further accelerated the spread of the fire.
Other factors that increased risk
- In responding to the fire alarm, not all of Ocean Drover’s crewmembers assembled at their emergency muster stations. As a result, not everyone was accounted for until about 1 hour after the fire started.
- Repeated single-person entries into the smoke filled accommodation were contrary to shipboard procedures and recognised rescue methods.
- The use of multiple berth cabins to accommodate the ship’s large complement of crew increased both the combustible material and ignition sources in each cabin.
- The smoking policy and associated risk controls on board Ocean Drover were not effectively managed. While use of designated smoking rooms was identified as the preferred option, smoking was permitted in cabins. In addition, approved ashtrays were not always used to extinguish and dispose of cigarettes. [Safety issue]
Other findings
- It was fortunate that the second mate’s selfless actions in rescuing a missing crewmember did not result in any adverse consequences.
- The timely response of shore fire and emergency services with available resources resulted in the serious fire being contained within Ocean Drover’s accommodation block.
- The ship’s crew received significant assistance from seafarer welfare organisations and others, including local community groups, in coping with post-fire trauma and losing their belongings.
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
The initial public version of these safety issues and actions are repeated separately on the ATSB website to facilitate monitoring by interested parties. Where relevant the safety issues and actions will be updated on the ATSB website as information comes to hand.
Bridge deck stairwell fire door
Safety issue number: MO-2014-012-SI-01
Safety issue description:
Ocean Drover’s bridge deck stairwell fire door was fitted with a holdback hook in contravention of international regulations. The door was hooked open, which allowed the fire to spread to the bridge deck from the deck below.
Smoking risk controls
Safety issue number: MO-2014-012-SI-02
Safety issue description:
Ocean Drover’s bridge deck stairwell fire door was fitted with a holdback hook in contravention of international regulations. The door was hooked open, which allowed the fire to spread to the bridge deck from the deck below.
Purpose of safety investigationsThe objective of a safety investigation is to enhance transport safety. This is done through:
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action. TerminologyAn explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue. Publishing informationReleased in accordance with section 25 of the Transport Safety Investigation Act 2003 Published by: Australian Transport Safety Bureau © Commonwealth of Australia 2016 
Ownership of intellectual property rights in this publication Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia. Creative Commons licence With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence. Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work. The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly. |
Preliminary report
Report release date: 15/01/2015
| This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003. |
Safety summary
What happened
On the morning of 9 October 2014, a fire started in Ocean Drover’s crew accommodation while the livestock carrier was berthed in Fremantle and preparing to load cargo. The fire quickly spread, and the ship’s crew and a number of the port’s emergency response teams fought to control it for the rest of the day. Four of the ship’s crew sustained smoke inhalation requiring medical treatment; one being hospitalised for smoke inhalation and burns.
By the time the fire was extinguished the following day, the accommodation areas and the ship’s navigation bridge had been extensively damaged.
What the ATSB has found so far
Initial analysis by the ATSB and the Western Australia Department of Fire and Emergency Services (DFES) indicates that the fire started in one of the central forward cabins on the upper deck. The fire quickly spread and engulfed both the upper deck and the bridge deck above.
Investigation direction
The investigation is ongoing and will focus on:
- the circumstances and mechanisms of the fire initiation and spread
- the operation and efficacy of the ship’s fire detection, protection and extinguishing systems
- crew training and shipboard emergency response.
Occurrence summary
| Investigation number | 315-MO-2014-012 |
|---|---|
| Occurrence date | 09/10/2014 |
| Location | Fremantle |
| State | Western Australia |
| Report release date | 11/03/2016 |
| Report status | Final |
| Investigation level | Systemic |
| Investigation type | Occurrence Investigation |
| Investigation status | Completed |
| Mode of transport | Marine |
| Marine occurrence category | Fire |
| Occurrence class | Accident |
| Highest injury level | Serious |
Ship details
| Name | Ocean Drover |
|---|---|
| IMO number | 9232852 |
| Ship type | Berthed |
| Flag | Singapore |
| Manager | Wellard Ships, Singapore |
| Departure point | Fremantle, Western Australia |
| Damage | Substantial |