On 12 October 2014, at about 1517 Central Daylight-saving Time, the flight crew operating a Qantas Airways B737 aircraft, registered VH-XZI, were preparing for the approach and landing into Adelaide, South Australia. The aircraft had departed about one and a half hours earlier from Alice Springs, Northern Territory, with the captain as the pilot flying (PF) and the first officer as the pilot monitoring (PM).
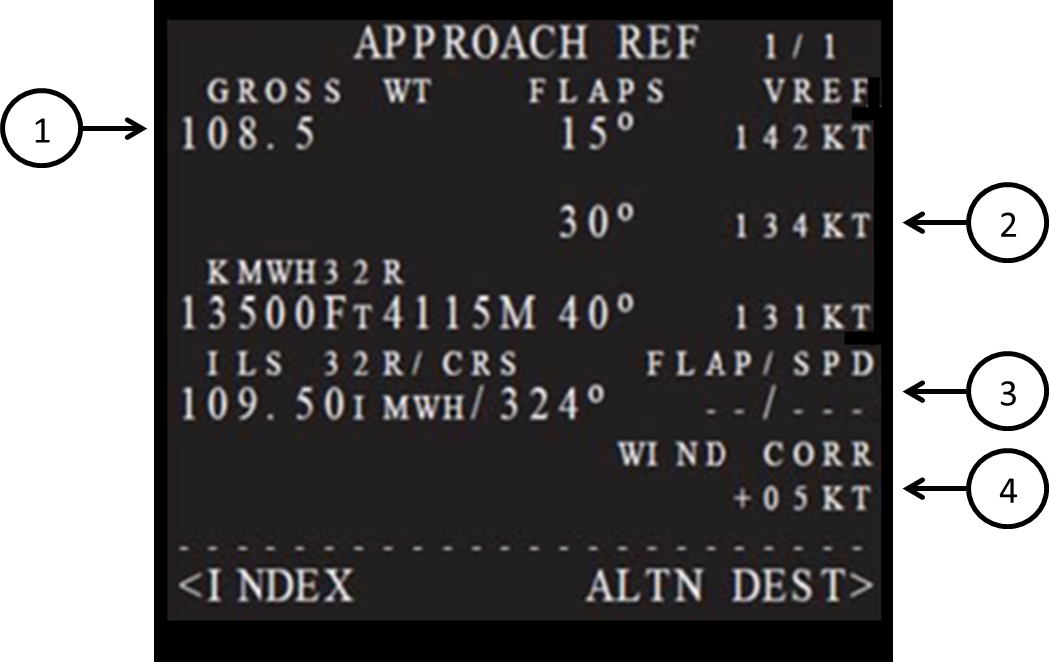
During descent preparations, air traffic control (ATC) issued arrival instructions which the crew loaded into the flight management computer (FMC)[1] via the control display unit (CDU)[2] (Figure 1). In accordance with company procedures, the PM calculated the expected landing weight. After obtaining confirmation from the PF that his calculations were valid, he entered this figure into the aircraft gross weight (Gross WT) section of the approach reference page, (Figure 1). However, according to the post-flight data obtained from the quick access recorder (QAR), a figure of 52 tonne (T) had been inadvertently entered instead of the predicted landing weight of 62 T.
To complete the manual selections, the PM stated he verbalised, and then selected the flap 30 field on the CDU (Table 1).
Figure 1: An example of a CDU Approach Reference page
Source: Qantas Flight Crew Training Manual
Table 1: Approach reference page expanded information
No.
Item
Function / notes
Detail
1
Aircraft Gross WT
Normally displays the FMC calculated aircraft Gross WT.
Manual entry of Gross WT is allowed. Leaving and returning to this page replaces a manually entered weight with FMC computed Gross WT.
2
Vref
FLAPS – VREF
Displays landing Vref for three flap settings as computed by the FMC. Speeds are based on displayed gross weights. Vref once selected, will not be updated. To obtain an updated speed, the current speed must be deleted, or a different Vref selected or entered.
3
Flap/Speed (FLAP/SPD)
Displays selected approach reference flap and speed setting.
Manual input of desired flap and/or speed settings may be made.
4
Wind Correction
Displays current wind correction for approach.
Default is +5 kt
Source: Qantas
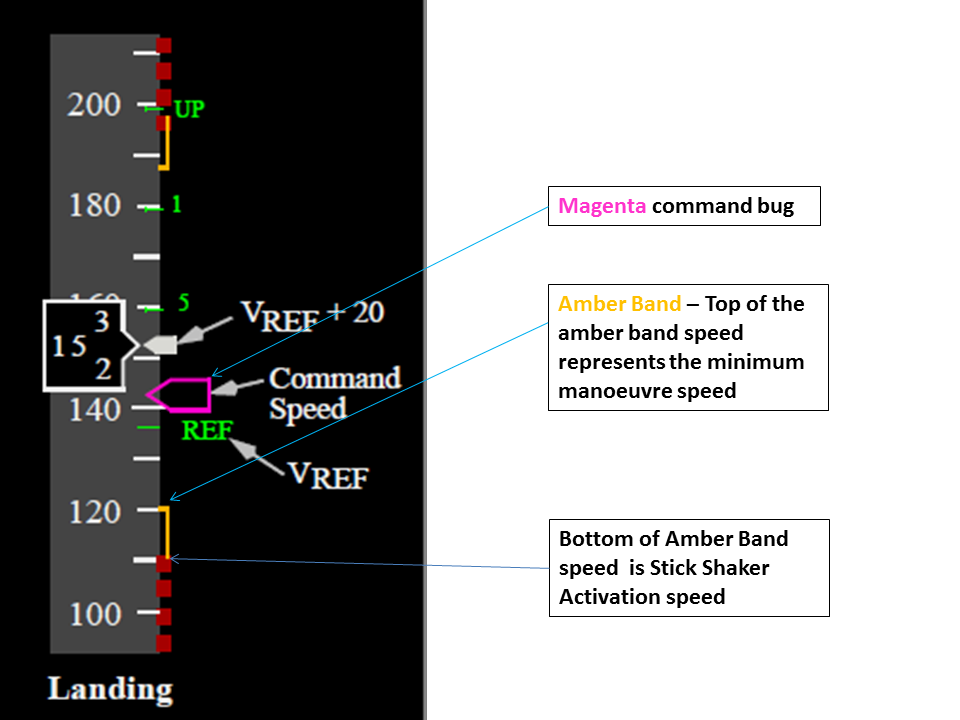
Following the inadvertent landing weight data entry error, the FMC calculated the flap speed schedule and the landing reference speed (Vref), based on this lower weight. With each stage of flap selection, the magenta bug[3] moved and pointed to the new command speed on the airspeed indicator. With the selection of flap 30, the command speed became Vref plus any wind correction factor entered by the crew[4] (Figure 2).
The captain briefed, then flew the arrival and approach onto runway 23 in clear conditions and mild, westerly winds. At about 1,500 ft above mean sea level, the aircraft was fully configured for landing with the gear down and flap 30. The captain disconnected the autopilot and hand flew the remainder of the approach and landing.
During the approach, the PM made a verbal reference about the airspeed being ‘wrong’. The PF reported he did not clearly hear what the PM had said, nor did he understand what message the PM was trying to convey. The captain assumed that the PM may have been making a comment in relation to a relatively new company procedure[5] used to calculate the approach speed. All the instrumentation presented to him looked normal, so he made the assumption that it was not something critical, and continued to focus on aircraft flight path management.
The PF continued to make adjustments to the thrust levers to allow for changes in wind. As was their normal procedure, the PF used the head-up guidance system (HGS) during the flight.[6] The PF reported that after the Flap 30 selection, he noted that the speed bug (‘magenta’ bug) moved a greater distance down the speed tape than normal, but he was not unduly concerned and continued to focus on flight path management.
At a height of about 200 ft, the PM reported he called “speed’ when he noticed the magenta speed bug on the primary flight display (PFD) airspeed indicator (ASI) reduce to within close proximity of the top of the amber band (Figure 2); however, the PF reported not hearing this call.
During touchdown, both crew noted that the aircraft’s pitch attitude was higher than usual. The aircraft had a nose-up pitch of 7.5°; whereas a normal nose-up pitch was 3.5-3.75°. The remainder of the landing was normal and there were no injuries and no damage to the aircraft.
The captain commented that with a non-VNAV approach, the crew set the approach speed into the mode control panel speed window (MCP). However, as in this case with a VNAV approach, the speed window is blank, the FMC selects the speed bug as the crew select the flap. This removed an opportunity for the crew to detect the speed mismatch.
The captain stated that in hindsight the aircraft nose attitude must have been higher than normal on the approach,[7] however he did not notice it during the occurrence.
First officer (PM) comments
When the PM noted that the magenta bug was closer than normal to the manoeuvring margin amber band on the PFD airspeed indicator, he thought the ‘moving’ amber band may have reached a higher airspeed due to the increased g loading in the gusty conditions, until he also noted the discrepancy on the CDU from the flaps 30 Vref calculated earlier during the preparation for descent phase.
The PM reported that when he made a reference about the airspeed being ‘wrong’, to the PF, he believed the call was clear and concise; he also added the instruction to fly a certain airspeed. He believed this was a safer option that going “head down” and reselecting the landing vref on the CDU.
As noted in Table 1 – note 1, once the crew left the approach reference page on the CDU and then returned to it, the page defaulted back to the FMC calculated (higher) GW and (higher) Vref for Flap 30. This realisation prompted the PM to say that the ‘speed’s wrong’ to the captain. When the PM saw the captain advance the thrust levers (for the gusty conditions) he thought this was a response to his comment.
Operator report
The operator conducted an investigation into the incident. Their report detailed the following:
The data entry error was made when entering the expected landing weight into the FMC Approach Reference page; this figure was not reconciled against the final load sheet
As the PM had only just started to comprehend the speed disparity, this led to the non-assertive comment. [note PM comment under First Officer comments regarding this aspect]
The Boeing Speed Calculation method may have contributed to a reduced level of recognition by the Captain of the significance of the position of the magenta bug and the amber band. This method varied from the previous Reference Ground Speed (RGS) method used to allow for changes in wind between when the aircraft was on approach and the wind experienced during touchdown
It is likely that the advancement of the thrust levels at the time the PM started to recognise a speed disparity led to a level of confirmation bias that the speed disparity was being addressed
The predicted landing weight was printed on the final load sheet given to the flight crew just prior to departure, however this figure did not allow for variations in fuel burn experienced in flight. The load sheet estimated landing weight was often used as a gross error check by flight crew, but it was not part of the company standard operating procedures. On this occasion, the crew did not conduct a gross error check using the load sheet figure, nor were they required to do so.
Non-technical skills training (NTS)
The operator reported that ‘flight crews undergo extensive non-technical skills training and recurrence during initial and cyclic training sessions. As part of this training, various levels of assertion are regularly highlighted in the event that a disparity in aircraft performance is recognised. Key indicators of uncertainty were observed in this occurrence around error recognition and confirmation. It is likely that this uncertainty resulted in a breakdown of the expected levels of assertion and a reduction in the preventative control’.
Recovery controls
The operator also noted that recovery controls would have been effective had the speed reduced to a critical amount. The head up guidance system provides visual caution/warning to the captain in the event that a tail strike pitch angle or rate is approaching, or has been exceeded. The head-up guidance system also indicates the angle of attack and normal angle of bank as a visual cue to the captain.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Flight operations
As a result of this occurrence, Qantas has advised the ATSB that they are taking the following safety actions:
Action taken by Qantas
As a result of this incident, the operator intends to revise the flight crew operations manual (FCOM) descent procedures. The procedures will include an item requiring the PM to compare the landing weight entered into the Approach Reference page during descent preparation, with the load sheet estimated landing weight.
Safety message
Data entry errors
Although having a primary focus on data input errors in preparation for take-off, the message is common. Errors can occur irrespective of pilot experience, operator, aircraft type, location and take-off [or landing] performance calculation method.
An ATSB research study titled Take-off performance calculated and entry errors: A global perspective is a research paper which focused on such incidents and accidents in the 20 years prior to 2009. A consistent aspect was the apparent inability of flight crew to perform ‘reasonableness checks’ to determine when parameters were inappropriate for the flight.
This research article is available at the ATSB website.
Also the ATSB have produced a short YouTube video on Safety concerns in regard to data input errors. This can be viewed at the ATSB website.
Crew communication
This incident highlights the importance of effective crew communication. The PM attempted to communicate his uncertainty to the PF, but the PF did not understand the specific nature of the PM’s concerns.
Non-technical skills (NTS) previously known as cockpit resource management (CRM) training has developed over many years to promote teamwork among pilots and to lead to a reduction in human error. Two studies conducted by Fischer, U., and Orasanu, J., published in 1999 looked at language and communication strategies between two groups of captains and first officers from three major US airlines. Of interest, the studies found that the strategies pilots indicated they would use to mitigate pilot errors, may not be the most effective ones. Also, there was a considerable difference between the captains’ and the first officers’ communication strategies.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope, fact-gathering investigation was conducted in order to produce a short summary report, and allow for greater industry awareness of potential safety issues and possible safety actions.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 21 October 2014, the pilot of a Eurocopter EC120B helicopter, registered VH-BGB, conducted a charter flight from a ship about 24 nautical miles north-north-west of Port Hedland to transfer two marine pilots to Port Hedland Airport, Western Australia. The flight was conducted under night visual flight rules.
At about 2240 Australian Western Standard Time, the helicopter lifted off and the pilot commenced the climb and transitioned to a forward airspeed of about 15 knots. As the helicopter passed over the bow of the ship, it encountered windshear. Approaching about 350 feet above sea level, the pilot observed the airspeed indicating about 5 knots. He reported that his focus had momentarily been on the radar altimeter, and he had not detected the airspeed decaying. He immediately applied forward cyclic to increase the airspeed, then continued the climb to 1,500 feet, and proceeded to Port Hedland without further incident.
The pilot reported that in a normal climb, by about 400 feet he would expect the airspeed to be approaching 40 knots. He believed that his delay in recognising the decreasing airspeed was due to feeling unwell. He had some symptoms of a cold prior to the flight, had been on duty for about 22 hours prior to the incident, and had slept for about 2 hours during that time.
The helicopter operator issued a Safety Notice to all company pilots reminding them of the importance of managing fatigue and fitness to fly in accordance with their Fatigue Management policy.
On 24 October 2014, the Melbourne to Sydney XPT service ST24 was approaching Culcairn station when there was a severe vibration. The driver stopped at the station and upon inspecting the train found that the axle had broken adjacent to the bearing box on the fourth passenger carriage. There were no injuries to passengers or crew. The passengers continued their journey to Sydney on chartered buses.
What the ATSB found
The ATSB found that the axle bearing had failed and completely seized, probably due to cage failure.
The probable cage failure caused the rollers to misalign and seize. This seizure of the rollers generated friction and excessive amounts of heat into the bearing journal. The heat applied to the bearing journal caused it to go ‘plastic’ and separate from the axle (commonly referred to as a screwed journal). In this case, much of the evidence was either lost or damaged beyond useful examination. Consequently, there was insufficient evidence available to determine why the bearing cage may have failed.
The ATSB also identified that ARTC train control, despite receiving reports of trackside fires, made contact with NSW Trains operations, rather than directly with the driver. It is unlikely that direct communication with the driver of ST24 would have resulted in a different outcome in this case because, by the time the potential cause of fires was known, ST24 was already on its way to Culcairn. However, in some scenarios, communicating directly with the train driver would likely ensure a more timely response to issues that may affect the safety of the network.
What's been done as a result
ARTC will ensure that all matters relating, or potentially relating to, the safety of a train operating on the network will be advised in the first instance to the driver of the involved train by the relevant Network Control Officer.
Safety message
Any issues with train services that can compromise the integrity and safety of the network must be communicated directly to the train driver. Communicating through a third party can compromise a timely response.
Source: Sydney Trains
The occurrence
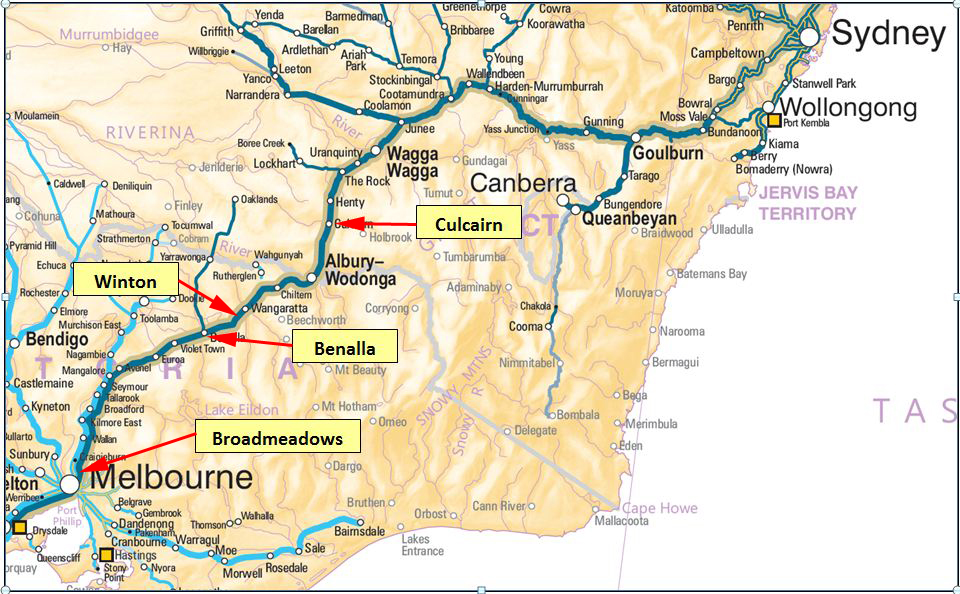
At about 0700[1] on October 24 2014, TrainLink[2] Sydney to Melbourne passenger service ST21, operated by NSW Trains,[3] arrived at Broadmeadows[4] Victoria (Figure 1). At Broadmeadows, there was to be a crew change and passengers disembarking the service.
As ST21 arrived at Broadmeadows, the relief driver, who was waiting on the platform, noticed what the driver described as a strong smell of brakes. During the handover briefing, the two drivers discussed the smell coming from the train. Although a smell coming from the brakes was common on long trips, the relieving driver, now in charge of the train, decided that he would undertake further inspection at McIntyre. McIntyre is located between Broadmeadows and Southern Cross station and was where refuelling of the return service to Sydney occurred.
At McIntyre, the train was re-fuelled and cleaned in readiness for the return journey to Sydney, with a new train identification number of ST24. While re-fuelling, the driver also examined the area of the train thought to be the source of the smell, paying particular attention to the brakes. While he again noticed the brake smell, he did not consider it unusual for a train having just completed a trip from Sydney. He then readied the train, departed McIntyre and arrived at Broadmeadows at about 0835 to pick up passengers. At about 0855, train ST24 departed Broadmeadows for Sydney with 125 passengers and crew on-board.
Figure 1: Location of Broadmeadows, Benalla, Winton, and Culcairn.
Source: Geoscience Australia annotated by the ATSB
At about 1041, ST24 arrived at Benalla station, stopping briefly to set down and pick up passengers. At about 1106, ST24 undertook another passenger stop at Wangaratta before continuing on to its next scheduled stop at Albury.
At about 1123, the Emergency Service Telecommunications Authority (ESTA known as ‘000’) received a phone call from a member of the public, advising of a fire between the Hume Hwy and the railway line about 5 km north of Benalla. After confirming the location, the operator dispatched the Country Fire Authority (CFA) to attend the scene. For the next 20 minutes, passing motorists and members of the public in the Benalla Winton area, reported more spot fires to 000.
At about 1143, the Australian Rail Track Corporation (ARTC) Train Transit Manager (TTM) at Junee Train Control Centre, NSW received a call from the CFA. The CFA reported that a fire in the Winton area was adjacent to the railway line.
Soon after, ST24 arrived at Albury station to set down and pick up passengers, then departed Albury for Culcairn at about 1153.
At about the same time, the ARTC TTM received another call from the CFA reporting that crews were attending the trackside fires. The CFA suggested that the last train through the area (about 30-45 minutes prior) had started the fires. The TTM advised that, at about 1100, a northbound passenger train (ST24) had passed through that area. The CFA re-affirmed their belief that this train had started the fire, as no other fires had been reported anywhere other than the Winton area. The TTM advised that he would contact TrainLink operations in Sydney and get them to make enquiries with the driver of ST24 about its possible connection with the Winton fires.
The TTM contacted the NSW Trains Daily Operations Continuity Centre (DOCC) Operations Manager and informed him of the fire in the Winton area. The TTM explained that the only train through that area in the last 50 minutes was the XPT Melbourne to Sydney service ST24 and that this train may have caused the fire. The Operations Manager informed the TTM that he would contact the driver of ST24 and make further enquiries regarding any problems with the train.
At around 1200, the NSW Trains Operations Manager contacted the driver of ST24 to inform him of a fire in the Winton area. He told the driver that the TTM in Junee had contacted him after they had received a report from the CFA regarding a fire adjacent to the track in the Winton-Benalla area. He told the driver that they believed his train had started it and asked if he had any issues with his train. The driver reported that everything seemed to be okay, but would inspect his train at his next scheduled stop.
The DOCC Operations Manager then contacted the TTM and informed him that he had spoken directly to the driver of ST24 and the driver reported nothing wrong with his train. He also advised that the driver would check it at the next scheduled stop.
At about 1213, the driver of ST24 experienced what felt like a run-in,[5] which he considered unusual for the approach into Culcairn. At about the same time, the driver heard (over the radio) the Passenger Attendant (PA) report to the Passenger Services Supervisor (PSS) of a severe vibration in the first class passenger car. Shortly thereafter, the PSS contacted the driver and advised that something was wrong with the first class passenger car. The PSS described it as a severe vibration, as if the passenger car was running over something.
At this stage, ST24 was approaching Culcairn. The driver determined that the train was still coupled and on the rails, so he decided to continue on the short distance to Culcairn.
At about 1216, the driver stopped the train at the station and notified Train Control (TC) that he was in clear[6] at Culcairn. He also advised that he was going to inspect the train, as the PSS had reported vibration in a passenger car. He asked for the departure signal to be placed at stop and asked for permission to access the track to inspect the train.
After inspecting the train, the driver notified TC that the trailing axle on car B (XL2235) had sheared off (Figure 2). He informed TC that the train was unable to continue its journey and alternative arrangements would be required for passengers to continue their journey. During the conversation, TC informed the driver of other reported fires in the Albury and Gerogery areas.
Figure 2: Failed axle and swing arm hanging down.
The image shows the failed axle journal, commonly referred to as a ‘screwed journal’. As the bearing housing no longer supports the axle, the swing arm has dropped. Source: NSW Trains, annotated by the ATSB
Events post-derailment
Passengers continued their journey on buses. The Australian Rail Track Corporation (ARTC) and NSW Trains examined options for moving the train to a siding at Culcairn. Once a suitable solution was identified, the damaged car was moved to the siding where it remained until arrangements could be made to replace the defective bogie. The remainder of the train then continued to Sydney.
It is likely that a progressively failing bearing on ST24 caused a number of fires beside the track. The fire services attended the fires, while the police attended the scene at Culcairn.
The ARTC arranged for an inspection to ensure the track had not been damaged by the dragging swing-arm. There was no damage to the track infrastructure.
The failed axle occurred near Culcairn (NSW), about 357 km [7] from Melbourne (Figure 1). The line, referred to by Train Control Junee as Main Line South, forms a main arterial link between Sydney and Melbourne.
The first reported fire occurred near Winton in Victoria (Figure 1) located at about the 207 km point.
Train information
The Express Passenger Train (XPT) is a ‘push-pull’ configured train with a power car at each end of the consist. The XPT was introduced in 1982 and is based on the InterCity 125/Class 43 design used in Britain.
Figure 3: XPT TrainLink power car XP2001.
The image shows an XPT power car and passenger car. ST24 consisted of five passenger cars, identified by the letters A-E, with a power car both leading and trailing. Source: ATSB
Sydney Trains owns the XPT fleet. NSW Trains is the operating agency providing passenger services through country NSW and to Brisbane, Canberra, and Melbourne.
The XPT train (ST24) consisted of a 5-car set with power car XP2001 leading and XP2016 trailing.
Train crew information
At the time of the incident, there were seven train crew on board, including the train driver. The driver of ST24 had over 13 years driving experience with 7 years driving XPT trains. The driver was tested for drugs and alcohol, and returned zero readings.
Train handling
The XPT power cars are fitted with Hasler tape data logging devices. Hasler data loggers record:
time, speed, distance
throttle position (power/idle)
vigilance acknowledgement
brake cylinder pressure.
Of the two devices, the data logger in XP2016 (trailing car) was fully functioning. The recording for the leading power car, XP2001 was incomplete in that it did not record distance or brake cylinder pressure correctly.
The data logged from XP2016 was validated against train control graphs for distance travelled. The brake cylinder pressure could not be validated against XP2001 data logger. However, the recorded brake cylinder pressures changes indicate a consistent deceleration pattern with similar changes seen in the recorded BCP during all braking sequences on XP2016.From the evidence available, it was determined that the train handling was generally consistent with common train handling practices.
Refuelling
The XPT trains require mid-journey refuelling for the service from Sydney to Melbourne and return. During the re-fuelling at McIntyre, the driver of ST24 also looked for any issues that may have caused the brake smell observed at Broadmeadows.
Due to the train’s position, it was not safe to check its left hand side (in the direction of travel to Sydney) because of the adjacent live track. However, the driver did check the right hand side of the train, checking cars A, B, and C (Melbourne end - last three carriages). During these checks, the driver did not see any signs of the journals or bearing boxes being abnormal but noted that there was a smell and the brakes were warm. However, the driver did not think it was out of the ordinary, as the train had just completed a journey of over 1000 km.
Track information
The Main Line South track is a standard gauge track[8] consisting of continuously welded rail on concrete sleepers, fastened by resilient clips.
The ARTC lease and manage the track. Control for the Main Line South signalling is from the ARTC Train Control Centre at Junee.
Track speed approaching Culcairn station is 160 km/h for XPT services. The service only stops at Culcairn when passengers are scheduled to disembark or board the service.
Bearings
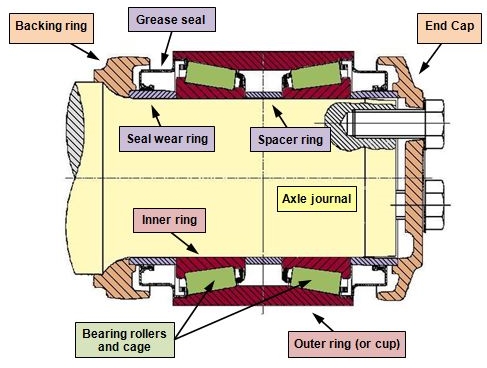
The bearings used on the XPT fleet are Timken SP120 package tapered roller bearing. Package bearings consist of two tapered bearing assemblies (commonly referred to as cones, and includes the inner rings, rollers and cage). Between the two bearing assemblies is a spacer ring of specific width, correctly positioning the two cones when the bearing is assembled. Outside each bearing assembly is a seal wear ring, over which the grease seal is positioned. When installed in the wheel-set, a backing ring is mounted on the inboard side of the axle journal and an end-cap is bolted onto the outer end of the bearing journal (Figure 4).
Figure 4: Package bearing components
Source: ATSB
The Engineering Instruction for TrainLink wheelsets requires the bearings to be put into service within two years of manufacture or requalified date. If the date is more than two years, the bearings are required to have the grease replaced.[9]
Package bearings are installed as fully greased sealed units and are press fitted onto the journal at Unipart UGL in Auburn. The bearings do not require in-service regreasing, which reduces the risk of inadequate, excessive, or contaminated lubricant during operation.
Bearing history
Timken bearings supply new SP120 bearings to Bearing Engineering Services[10] (BES), which then supply UGL Unipart bearings for the XPT fleet. BES also service and requalify bearings for reinstallation.
Combinations of new and requalified bearings were installed on passenger car XL2235. The new bearings were manufactured in South Africa in 2012. These bearings were supplied to UGL with Renolit MP3 grease, as installed by the manufacturer. The requalified bearings were overhauled in 2013 (by BES) and supplied to UGL with Timken premium railroad grease.
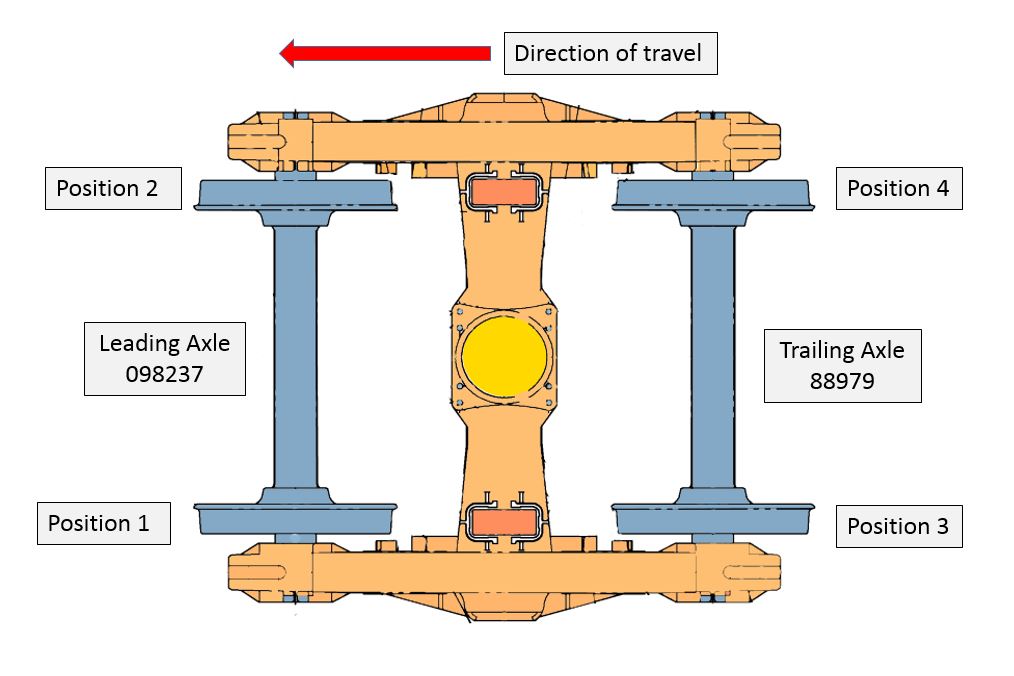
The bearing installed into position 3 (Figure 5) on bogie NHA-8B in June 2014 was a new bearing. The serial number of the bearing was 302379 with a manufacture date of July 2012.
At the time of its failure, the bearing was well within its service life of 375,000 km.[11]
Figure 5: Bearing position on bogie NHA-8B
Source: ATSB
Bearing and axle examination
The bogie was taken to the UGL Unipart in Auburn for examination. Preliminary examination of the failed bearing components by the ATSB indicated that the bearing had seized. The remains of the bearing and the accompanying swing arm were taken back to ATSB laboratory for further analysis. The remains of the axle journal were not recovered.
It was evident that the bearing had seized while the axle was still turning. The heat generated by the failed bearing was sufficient to heat the journal, to make it ‘plastic’ (Figure 6) and cause it to separate from the axle (commonly referred to as a screwed journal).
Figure 6: Swing-arm bearing housing
The XPT bogie swing-arm bearing housing, viewed from the inboard side. The heat damage is evident and the remaining bearing components can be seen inside the housing. Source: ATSB
The ATSB failure analysis specialists conducted an examination of the failed bearing. Witness marks at the interface between the bearing and the swing-arm bearing housing could not be examined due to the extensive damage to the bearing.
There were a number of flat rollers on the inboard (Figure 7-1) and the outboard (Figure 7-3) bearings. Markings on the flattened rollers indicate that the rollers seized and misaligned in the bearing cage while the axle was rotating.
The inboard raceway showed evidence of full-width spalling[12] fatigue (Figure 7-2). The spalling fatigue began from the 6 o’clock position and continued in the direction of rotation to the 9 o’clock position. There was also some fracturing of the shoulders on the unworn surfaces of the track.
The outboard raceway showed a full-width area of galling[13] and deposited metal (Figure 7-4). Galling is usually associated with a lack of lubrication, resulting in the two metal surfaces welding together for brief periods.
The investigation also examined the partner bearing from the opposite end of the axle.
The partner bearing was removed from the journal and the end cap bolt torque measured. The torque values were consistent with the maintenance requirement. Initial observations indicated that the partner bearing was generally in good condition.
Partner bearing examination by BES
BES conducted an examination of the partner bearing, with the ATSB present.
The bearing was weighed and grease samples from the inner, outer and spacer (centre) of the bearing was taken and sent for analysis. The BES examination found that the bearing showed uneven adaptor fretting[14] marks on the cup exterior (Figure 8-1). There was also wear and damage to the inboard raceway (Figure 8-2) and outside edges of the inboard cone rolling elements (Figure 8-3). Conversely, the raceway and rolling elements of the outboard cone (Figure 8-4) were in good condition.
Based on the amount of fretting on the bearing cup BES concluded that the bearing was probably misaligned (unevenly loaded) from when the bogie was put into service.
Figure 8: Partner bearing
Image 1: Uneven fretting marks on the exterior of bearing cup indicating uneven contact pressure between the bearing cup and the swing-arm bearing housing. Image 2: Indentation damage to the inboard raceway. Image 3: Peeling damage to the rolling elements of the inboard cone, predominately on the outside edges due to uneven loading. Image 4: Undamaged rolling elements from the outboard cone. Source: BES
During the BES examination, ATSB investigators took grease samples from the partner bearing for analysis. After the BES examination was completed, ATSB investigators retained the partner bearing for further analysis.
Partner bearing examination by the ATSB
An ATSB failure analysis specialist examined the partner bearing components using an illuminated magnifier and with a stereomicroscope.
Outer cone
The outer cone had limited wear with fine brinelling,[15] scoring and polishing. This wear was also evident in the analysis of the grease samples. The samples contained iron but not chromium from alloy steel (the rollers, cup, and cone). The wear had mostly come from the soft, plain-carbon steel cage.
Inboard cone
The results of the inboard cone analysis contrasted with that of the outboard cone, with significantly higher presence of chromium from the alloy steel cup, cones and rollers.
The examination found evidence of metal loss to the bearing spacer and inner rear enclosure. The wear on the spacer would likely have resulted in some loss of preload on the bearings resulting in excessive end float. Increased end float would have placed uneven loading on the bearing, in particular the back-face end of the inner cone/double cup. It is possible that this point on the partner bearing acted as a fulcrum when the axle journal failed and the opposite end of the axle became unsupported.
The rollers of the inboard cone showed evidence of adhesive wear, but only at the back-face end. This corresponded with the inboard raceway, which exhibited a worn shoulder with several bright areas of spalling.
Swing-arm Bearing Housing
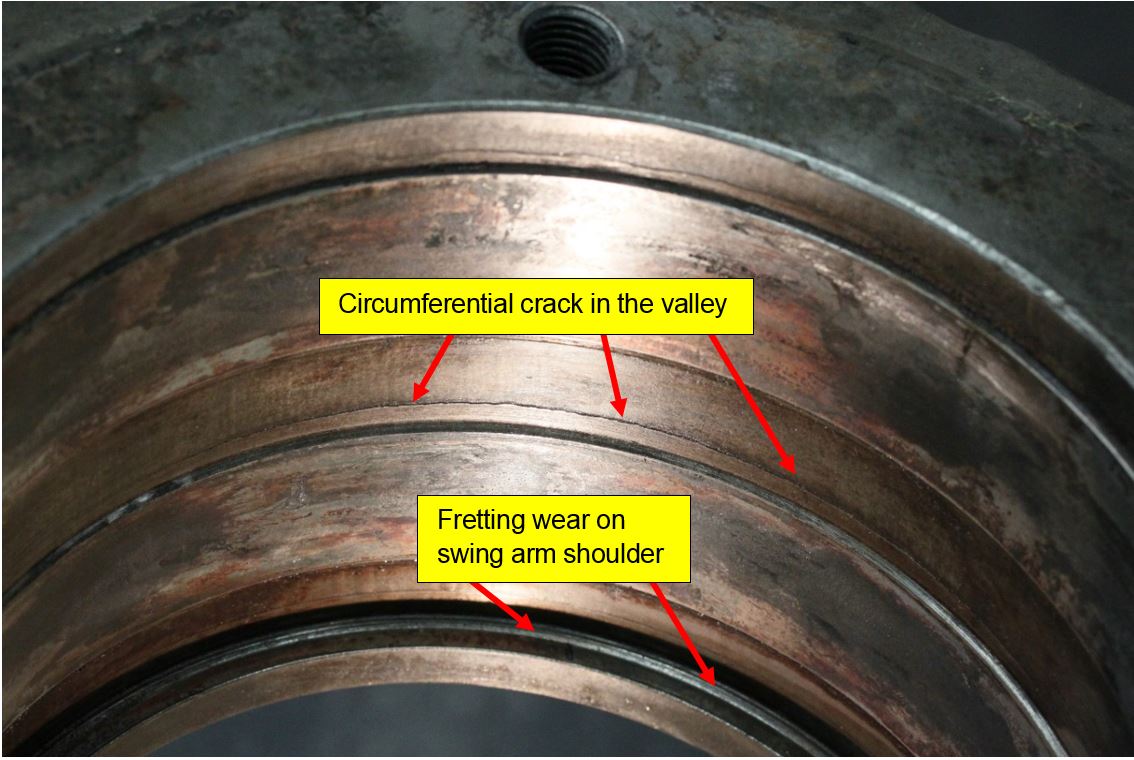
The swing-arm bearing housing showed heavy fretting wear that corresponded with asymmetric fretting wear on the bearing cup (Figure 9). Also observed, was the crack in the upper half of the bearing housing (Figure 10).
Figure 9: Partner bearing (position 4) serial number 302111
The corresponding fretting marks found on the partner-bearing cup was also evident on the partner swing arm. Source: ATSB
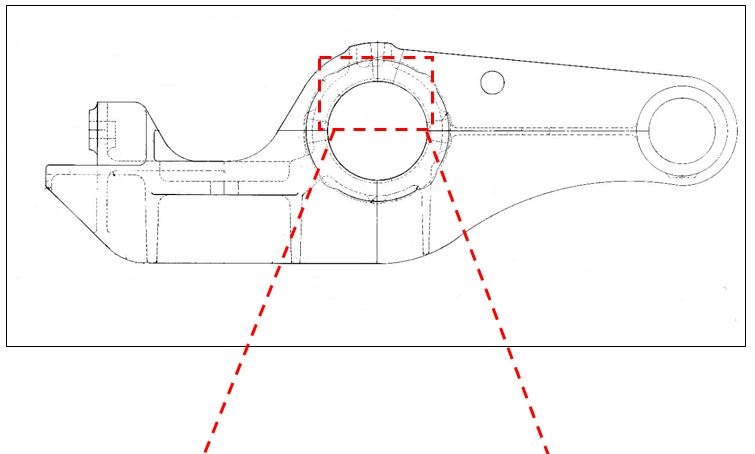
Figure 10: Swing arm assembly with exploded view of the bearing housing bore below
Figure 10 is of the partner swing arm (from the same axle). The exploded view shows the fretting wear on the swing arm shoulder evident by the shiny marks as annotated. As illustrated, there is also a crack in the valley of the housing. Source: ATSB
These wear patterns provided further evidence of uneven loading, possibly due to the axle misaligning when the axle journal failed and the opposite end of the axle became unsupported.
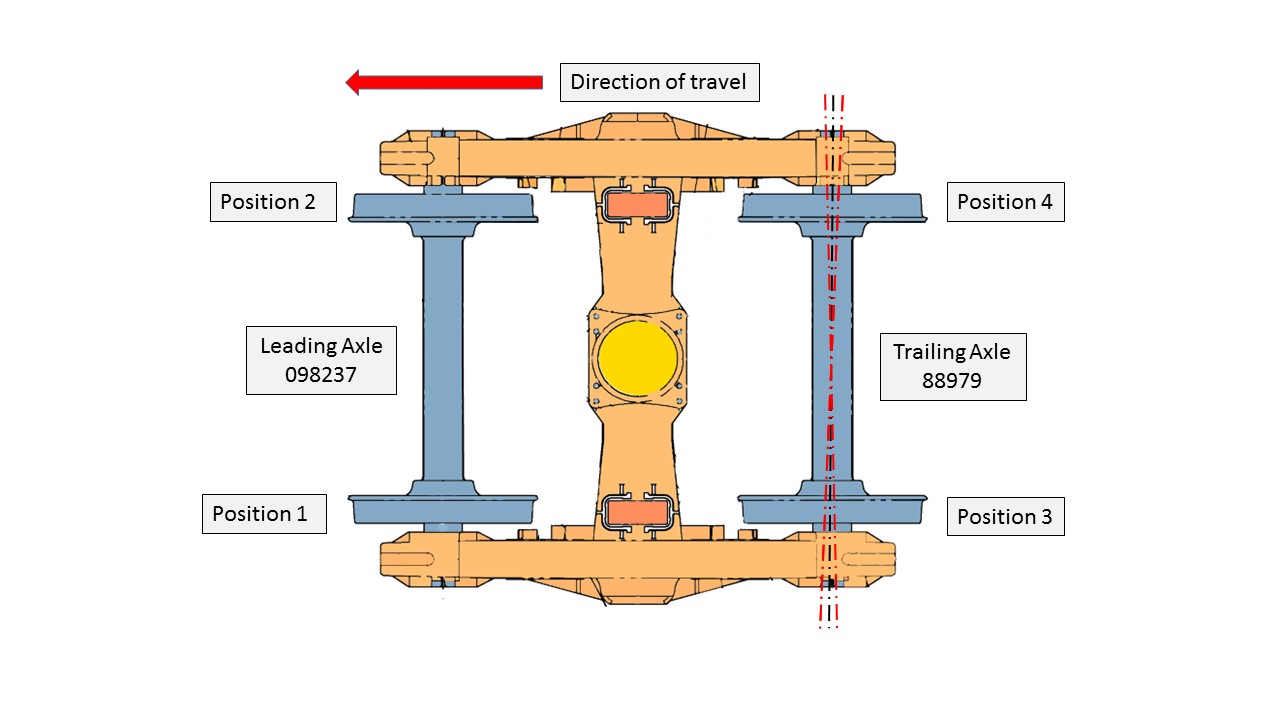
When matching the bearing cup witness marks to those in the swing-arm bearing housing, the marks ranged from a 9-3 o’clock position and were asymmetric in nature. This indicated that there might have also been some misalignment in the horizontal plane (Figure 11).
Figure 11: Bearing position on bogie NHA-8B
Figure 11 is for illustrative purposes and not a direct representation of an XPT bogie. The black dotted line on the trailing axle represents the centreline of the axle when running true. The red line illustrates a misalignment of the trailing axle, in the horizontal plane. Source: ATSB
The ATSB concluded that there was evidence of uneven loading. However, there was insufficient evidence to determine if the misalignment was predominantly in the horizontal or vertical planes.
When considering the physical evidence and examinations by both BES and ATSB specialists, the most likely conclusion is there was a misalignment in the axle. However, there was insufficient evidence to determine if this was a pre-existing condition or if it occurred because of the bearing failure.
There were no conditions associated with the partner bearing (position 4) that would suggest a possible cause for the failure of the bearing in position 3.
Grease analysis
The type of grease used by Timken in the new bearings is Renolit MP3 grease. The operator’s Engineering Standard for grease used in journal bearings for seal and package units requires that the grease be approved by the Association of American Railroads (AAR). Renolit MP3 grease is not approved by the AAR in this application. However, the grease has almost identical properties to that of an AAR approved grease type such as Timken premium railroad grease. There is no evidence that the use of Renolit MP3 grease contributed to the failure.
Partner bearing grease analysis
The partner bearing grease samples were sent to the ALS Laboratory Group for analysis. The results showed a mid-range content of silicon (contaminant) and higher levels of iron from the centre (spacer ring) grease sample, mid-range chromium and silicon with higher levels of iron from the inboard sample and low levels of chromium with mid-range levels of silicon and higher levels of iron from the out-board sample.
The chromium levels from the inner and outer grease samples indicate that it was liberated most likely from the inner and outer cup and because of the peeling damage from the inboard cone roller faces. Indentation marks on the inner and outer race was evident from the BES report and ATSB analysis.
The iron found in all three samples is likely to be from the roller cage as a result of the axle failure placing more stress on the partner bearing.
Although the grease analysis showed high levels of contaminants and iron it is likely this is due to the failed axle.
Examination of the partner bearing grease found no condition or anomaly that could be directly related to a potential issue with the corresponding failed bearing.
Bearing failure types
The recovered bearing components were examined in relation to the common failure modes for railway bearings.
A loss of interference fit between the bearing and axle journal often occurs later in the failure sequence. That is, other faults may combine to cause progressive loss of interference fit. Initial slippage may be small, but as the journal wears, the amount of slippage increases.
However, if a bearing seizes, slippage of the inner ring on the journal can suddenly occur.
Lubrication failure
The function of a lubricant is to separate the rolling contact surfaces at the point of high-pressure contact. The lubricant film between the surfaces acts to reduce wear, friction and corrosion such that the bearing should achieve its predicted fatigue life; assuming that no other factors exist that may cause premature failure. Lubrication failure can occur due to an inappropriate grade of lubricant, insufficient lubricant or contamination of the lubricant.
Cage failure
The bearing cage is designed to retain the rollers within the bearing in a consistently spaced and correctly aligned position. The cage has no role in the transmission of forces. The cages in bearings used in the railway industry are usually pressed out of metal plate.
The purpose of roller bearings is to avoid sliding friction. However, sliding at the cage surfaces cannot be avoided. Consequently, the softer material of the cage (when compared to other components) is likely to be the first area to wear when lubrication becomes inadequate or foreign material causes abrasion. Once wear occurs, the cage loses the ability to align the rollers correctly and leads to a rapidly deteriorating cage resulting in a complete failure of the cage. Once the cage fails, material jams the rollers, generating heat and the bearing inevitably fails.
Bogie NHA-8B maintenance
UGL Unipart, located in Auburn NSW, is the contracted maintenance provider for XPT bogie refurbishments. XPT carriage bogies are overhauled every 750,000 km with the wheelsets overhauled every 375,000 km. New or requalified[16] bearings are fitted with the changed out wheelsets.
The ATSB examined the maintenance records of bogie NHA-8B. The records show that during the assembly and overhaul of the bogie, all components and relevant measurements meet the requirements of the XPT carriage NHA Bogie Overhaul Specification RX01_0200_123MP.
In June 2014, passenger car XL2235 had the overhauled bogie NHA-8B fitted to the B end of the passenger car. The failed axle of the bogie set (the trailing axle in this case) had new bearings installed. The lead axle assembly had requalified bearings.
In-service inspection and maintenance
XPT carriages undergo trip inspections either at 2-day intervals or at 3000km, and maintenance every 90 days.[17] Both inspection intervals include the testing of axle box temperatures (by feel) as the train is being fuelled and decanted.
Axle boxes are also inspected for:
loss of lubricant at rear axles seals
discolouration indicating overheating.
During the operation of carriage XL2235 on 15 August 2014, a defect was noted on bogie NHA-8B on the power car logbook[18]. The defect was reported as a ‘whirring’ noise from beneath the car and the axle boxes were warm to touch. The defect was inspected on the next scheduled service on 16 August 2014 and no issue was found. The carriage was returned to service without any further noted defect regarding whirring noises or warm axle boxes.
The last documented trip inspection was on 23 October 2014 with no issue recorded. Analysis of the maintenance documentation including the defect history and inspection records indicated that there were no pre-existing maintenance issues identified with bogie NHA-8B.
Condition monitoring systems
Condition monitoring systems can be split into two generic types, reactive and predictive. These are akin to reactive and preventative maintenance. A reactive approach requires an immediate action after a serious condition develops or equipment failure occurs, whereas a predictive/preventative approach identifies the requirement for future action before a serious condition develops.
Reactive condition monitoring, such as hotbox detectors, are usually used as a ‘last line of defence’ to protect significant or critical railway infrastructure assets. They are usually used on track associated with production processes such as coal and ore carrying railways, but less common on mixed freight/passenger tracks such as the interstate main lines (refer to appendix A).
In this case, there were no reactive condition monitoring systems in place that could have detected the imminent failure of the bearing on XPT service ST24.
Infrastructure managers and rolling stock operators have directed more effort towards predictive condition monitoring of railway rolling-stock travelling on the interstate main lines. With regards to bearing condition monitoring, the predictive systems adopted are Bearing Acoustic Monitoring (BAM) systems (refer to appendix A).
Being a predictive condition monitoring system, multiple passes of potentially defective bearings are required for trends to be clearly identified and actioned before a defect reaches a critical level. Consequently, the systems are positioned throughout the interstate network based on major rail corridors. For the Sydney-Melbourne corridor, the BAM system was located on the Main South up line at Exeter, NSW (about 155 km from Sydney).
Examination of the BAM data for XPT passenger car XL2235 found no evidence of acoustic signatures to suggest the onset of a bearing failure.
In this case, much of the evidence that may have indicated the cause of its failure was either lost or damaged beyond useful examination. However, the absence of BAM data indicating a developing bearing fault would suggest that the bearing on XL2235 experienced a relatively quickly developing fault resulting in catastrophic failure. Consequently, failure modes such as metal fatigue, rolling surface defects and loose bearing components are less likely to have been failure initiators.
Examination of the partner bearing provided no clear indication of a failure mode that may have resulted in the failure of the bearing on XL2235. However, some iron particles where found in the grease indicating wear on the bearing cage. There was also evidence of uneven loading due to misalignment of the axle. However, there was insufficient evidence to determine if this was a pre-existing condition or if it occurred because of the bearing failure.
As most failure modes were considered less likely, the most probable cause of the bearing failure was a cage failure. The cage failure caused the bearing rollers to become misaligned and subsequently seize in the bearing housing. The seizure then caused friction resulting in excessive heat to build up in the bearing housing within the swing arm and journal. This generated enough heat into the bearing journal to cause it to go ‘plastic' and separate from the bearing journal.
Bearing cages may fail due to lack of lubrication, bearing misalignment (uneven loading), shock loading (wheel impacts), or a combination of these conditions. In this case, there was insufficient evidence available to determine why the bearing cage may have failed.
Reports of trackside fires
While in Melbourne, the driver of XPT train ST24 noticed a strong smell typical of hot brakes. The driver inspected the train before departure, but found nothing of concern. The investigation found no other precursor events or conditions that might suggest imminent failure of a bearing on XPT car XL2235 prior to its departure from Melbourne. However, there were events reported during the journey that may have suggested a potential problem with XPT train ST24.
After the passage of ST24, several fires were reported to the fire authorities, which required fire crews to attend.
The first report to the ARTC train control centre was of a fire in the Benalla-Winton area. Soon after, train ST24 arrived at Albury, set down and picked up passengers, then departed Albury for Culcairn. At about the same time, the Country Fire Authority made a second call to the ARTC.
The reported fires were all in close proximity to the track, suggesting that a train had started them. The timing and sequence of the reports suggested that train ST24 had started the fires, as it was the last train to have travelled through that area. It is likely that the failing bearing liberating hot components that consequently started the fires.
Following the second call from the Country Fire Authority, the ARTC TTM contacted the NSW Trains operations manager to advise that there may be a problem with their TrainLink service ST24, and requested them to check their train.
County Link operations contacted the driver of ST24 as he was travelling through the Table Top area advising him of the fire in the Benalla-Winton area. About 15 minutes had passed between the first report to train control and the request for the driver to check the condition of train ST24.
The North Albury and Gerogery fires were reported to train control when ST24 was already at Culcairn. There were no other fires reported on the Main Line South between Winton/Benalla and Sydney for that period.
It is likely that heat generated by a progressively failing bearing on ST24 had started a number of trackside fires. While the fires were reported to train control, there was no direct communication with the driver of ST24.
Communications between train control and ST24
TrainLink XPT trains have mobile phones fitted to every power car that use the Telstra mobile network.
An examination of phone records show that the calls made to the lead power car of ST24 were from the NSW Trains Daily Operations Continuity Centre (DOCC) in Sydney. Phone records obtained from ARTC and Sydney Trains confirm that at no stage prior to the axle failure did ARTC train control contact the driver of ST24.
ARTC Emergency Management
ARTC has an emergency management procedure (TA44) which outlines the management of emergencies within the ARTC rail network. The procedure addresses trackside fires and the management of the network and trains that may be affected by that fire. In short, the Train Transit Manager (TTM) or nominated representative takes the role of the Incident Response Coordinator, responsible for advising the relative parties such as emergency services and train operators of the incident.
In this case, the TTM assumed the incident response coordinator’s role when advised of the fire in the Benalla-Winton area. The TTM then liaised with the CFA control centre to ascertain the position of the fire and if CFA officers were on or near the track.
With respect to a fire in or near the rail corridor, it was evident that the procedures documented in procedure TA44 were intended to manage potential damage to infrastructure, and to manage the risks associated with fire crews working near the rail track. The procedure did not include consideration of the potential cause of a fire.
Requirements under Network Rule ANTR 402
Network rule ANTR 0402 ‘Inspecting trains’ covers inspecting of trains during travel in NSW. The Inspection during travel rule states that:
If unsafe conditions or defects are reported to Network Control, a Network Control Officer must:
Tell the affected Train Crew about unsafe conditions and defects, and
Follow the requirements of Rule ANGE 206 Reporting and responding to a Condition Affecting the Network
An equivalent requirement is not specifically documented in the rules applicable to Victoria.
In this case, the ARTC received advice from the CFA that they believed a train that had started the fires at Winton. By this time, ST24 had just departed Albury and was travelling towards Culcairn. The ARTC contacted a third party (DOCC) requesting a check of train ST24, rather than directly contacting the train crew.
It is unlikely that direct communication with the driver of ST24 would have resulted in a different outcome in this case because, by the time the potential cause of fires was known, ST24 was already on its way to Culcairn. However, in some scenarios, communicating directly with the train driver would likely ensure a more timely response to issues that may affect the safety of the network.
The ATSB identified a similar issue during another investigation.[19] In that incident, it was apparent that the use of a third party was common for facilitating communication between Network Control Officers and train drivers.
From the evidence available, the following findings are made with respect to the axle failure on XPT ST24 on 24 October 2014 at Culcairn NSW. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
The XPT axle failed when the bearing seized, generating enough heat for the bearing journal to go ‘plastic’ and separate from the axle, a condition commonly referred to as a ‘screwed journal’
In the absence of any evidence to the contrary, the most probable cause of bearing seizure was failure of the bearing cage. This likely allowed the rollers to misalign and jam, resulting in slippage of the inner bearing ring on the journal.
Other findings
There was insufficient evidence available to determine why the bearing cage may have failed.
It is likely that a progressively failing bearing on ST24 caused the trackside fires reported to the ARTC train control.
On receipt of the initial advice of the fire at Winton ARTC promptly communicated with the NSW Trains Operations Manager. However, direct contact with the Driver of ST24 would have been more appropriate.
The grease used by the bearing manufacturer in the new supplied bearings was not an approved grease as documented in ESR 0400 Engineering Standard for bearing grease.
The Hasler data logger in lead power car XP2001 was defective in that it was not recording brake cylinder pressure or distance.
Safety actions
Additional safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Additional safety action taken by ARTC
ARTC will ensure that all matters relating, or potentially relating to, the safety of a train operating on the network will be advised in the first instance to the driver of the involved train by the relevant Network Control Officer.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Transport for NSW
Sydney Trains
UGL Unipart
Australian Rail Track Corporation
NHA-8B Bogie Overhaul maintenance documentation
XPT Power Car Log Books for ST24
Trailer car (XL2235) inspection sheets
BES Bearing Inspection reports for remanufactured bearings
References
Queensland Rail Train handling manual SRD/0063
XPT Trailer Car NHA Bogie Overhaul Specification RX01_0200_123MP Version 1.0
ESR 0400 Specification for the Journal Bearing Oil & Multi-Purpose Grease
Sydney Trains XPT Inspection Schedule & TMP Inspection Timetable
ASM Handbook, Volume11, Failure Analysis and Prevention
State Rail Authority Engineering Instruction EIDSS 5152 22 November 2004 issue 2
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Transport for NSW, Sydney Trains, the driver of train ST24, NSW Trains, Bearing Engineering Services, the Australian Rail Track Corporation, and The Office of National Rail Safety Regulator (ONRSR).
Appendices
Appendix A – Condition monitoring systems
Hot-box detectors
Hotbox detectors are a reactive method of condition monitoring. They usually detect the infrared signature of bearing components and alarm if the temperature exceeds a predetermined setting. However, there are a number of variables that can affect their performance on a mixed freight/passenger rail corridor. These variables include but are not limited to:
train loading
train speed
weather conditions.
Consequently, hotbox detection is usually used as a ‘last line of defence’ to protect railway infrastructure assets critical to production processes such as coal and ore carrying railways.
Due to the potentially unreliable performance of hotbox detectors under mixed freight/passenger conditions, more effort has been directed towards predictive condition monitoring of railway rolling stock travelling on the interstate main lines.
Bearing Acoustic Monitoring
Bearing Acoustic Monitoring (BAM) is a predictive condition monitoring system that ‘listens’ to the acoustic signature of bearings and can detect faults as they develop. It is the primary method for detecting potential bearing faults on rolling-stock travelling on the interstate main line. Recorded data from each train is stored in a database allowing evaluation, trending, and maintenance scheduling of rolling-stock based on predicted bearing condition.
BAM uses sensitive acoustic arrays to record the sounds emanating from wheels and bearings passing through the monitoring site. The recordings are processed for the sound characteristics that are unique to specific types of bearing faults. BAM is best at detecting faults on rolling surfaces such as the inner and outer raceways, and rollers in rolling-stock bearings. BAM can also detect looseness or fretting faults and ‘noisy’ wheels (flanging and wheel flats).
BAM systems are usually installed and maintained by infrastructure managers. However, the data is made available to rolling stock operators through a web interface. The BAM database categorises potential bearing faults in the form of levels of severity (1, 2, and 3 with level 1 being the most critical). The database allows operators to analyse bearing fault history and trends in order to plan their preventative maintenance strategies.
As for any monitoring system, there are some limitations. For example, BAM is a system that ‘listens’ for bearing noises, and under some conditions, other noises (rubbing equipment, tread defects or flanging wheels) may affect the results. However, being a predictive condition monitoring system, multiple passes of potentially defective bearings allows true fault trends to be clearly identified and actioned before a defect reaches a critical level.
It is evident that predictive condition monitoring and a pro-active approach by train operators has become an integral tool for managing the risk of bearing defects on freight rolling stock, especially in relation to rolling surface defects. For example, the ARTC BAM site at Nectar Brook showed a reduction in the number of level 1 rolling surface faults from about 0.5% in 2002 to about 0.05% in 2010. However, Level 1 looseness or fretting (LF1) faults have not experienced the same improvement. In 2002, LF1 faults were about 1.2%, reducing down to about 0.6% in 2005 before rising back to 1.0% in 2009 and 2010.
On-board condition monitoring
In the past, condition monitoring of rolling-stock has been the realm of trackside equipment (Hotbox, RailBAM, etc.), usually fixed at a specific geographical location. While predictive systems may provide a broader level of protection, reactive systems are limited to protection of equipment and infrastructure in the immediate vicinity.
The next evolution of condition monitoring would be one that continuously monitored each wagon for developing faults (predictive) and immediately communicated any critical conditions to the train drivers (reactive). This type of system is referred to as an on-board condition monitoring system. While various limitations (functional and economic) have prevented these systems being widely used on railway freight operations in the past, recent technological developments have now made the concept more attractive. However, at the time of this incident, only limited developmental work had been started within Australia.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Section 21 (2) of the Transport Safety Investigation Act 2003 (TSI Act) empowers the Australian Transport Safety Bureau (ATSB) to discontinue an investigation into a transport safety matter at any time. Section 21 (3) of the TSI Act requires the ATSB to publish a statement setting out the reasons for discontinuing an investigation.
On 24 October 2014, the ATSB commenced an investigation into a loss of separation assurance involving an Embraer EMB-135, registered VH-JTG, and an Airbus A321, registered VH-VWX, overhead Taroom Aerodrome, Queensland on 21 October 2014.
Examination of the information collected during the investigation indicated that the aircraft were assigned the same flight level on crossing tracks resulting in a loss of separation assurance. VH-JTG passed in front of VH-VWX and separation reduced to 6.6 NM (12 km). The lateral separation standard at the time was 5 NM (9 km) and there was no Short Term Conflict Alert (STCA) or other alert issued, including by the aircraft’s systems.
The ATSB did not identify any organisational or systemic issues that contributed to the incident and assessed that no safety issues would be identified through further investigation. On that basis, the ATSB has decided to discontinue its investigation.
On 23 October 2014, Genesee & Wyoming Australia (GWA) train 5DD2 departed from Kevin, a gypsum mine near Penong, South Australia. The train was loaded with gypsum destined for the port at Thevenard. Shortly after entering the Penong Junction to Thevenard section, the driver felt two severe jerks and noticed a loss of brake pipe pressure and an unusual amount of dust from the rear of the train. After the train was brought to a stop, the second driver walked back along the consist and found several derailed wagons and a section of damaged track.
What the ATSB found
The ATSB found that the track infrastructure was generally in poor condition, with the rail exhibiting substantial head wear. The poor track condition had also allowed a wide gauge condition to develop, allowing rolling stock wheels to track away from the rail web. As a result of the head wear, gauge widening and the wheel tracking position, the capacity of the rail to support the wheel loads had been progressively reduced. This condition ultimately resulted in the failure of the rail head during the passage of train 5DD2, with the consequent derailment and infrastructure damage.
It was evident from the ATSB’s investigation that defect monitoring and reporting was not being conducted as specified in the relevant Code of Practice. As such, awareness of the rail condition and deterioration was reduced and remedial maintenance actions were not being planned or implemented.
The ATSB also found that Genesee & Wyoming Australia’s maintenance oversight had been limited, allowing the track to deteriorate to a point where trains could not be run safely.
What's been done as a result
Following the derailment, the track maintainer (Transfield Services) has undertaken to increase track inspection detail, with a view to identifying areas of concern for assessment and remedial works. GWA advised that they undertook their own inspection of identified sections of track with an emphasis on gauge and cant, and identified other locations that presented potential for a derailment to occur under similar circumstances. This resulted in the application of temporary speed restrictions over the affected areas and the insertion of timber sleepers to maintain gauge.
GWA also advised that they will undertake a review of the processes and procedures applied to rail infrastructure maintenance and have requested more regular track inspection reports from the contracted infrastructure maintainer. The ATSB has been advised that upgrade works are scheduled to improve the track condition and reduce the associated derailment risk, with the majority of works to be completed in 2015.
Safety message
This incident illustrates the importance of rail maintainers effectively documenting and accurately reporting the condition of the track to the responsible owner/operator. Similarly, owners and operators must maintain diligent oversight of infrastructure maintenance activity, particularly in areas where the track condition is known to be poor or deteriorating.
The occurrence
At about 0230[1] on 23 October 2014, the crew for Genesee & Wyoming Australia (GWA) train 5DD1 signed on for duty at Thevenard, South Australia. The train was scheduled to travel empty from Thevenard to the Gypsum Resources Australia mine at Kevin (Figure 1), to be loaded with gypsum before returning to Thevenard.
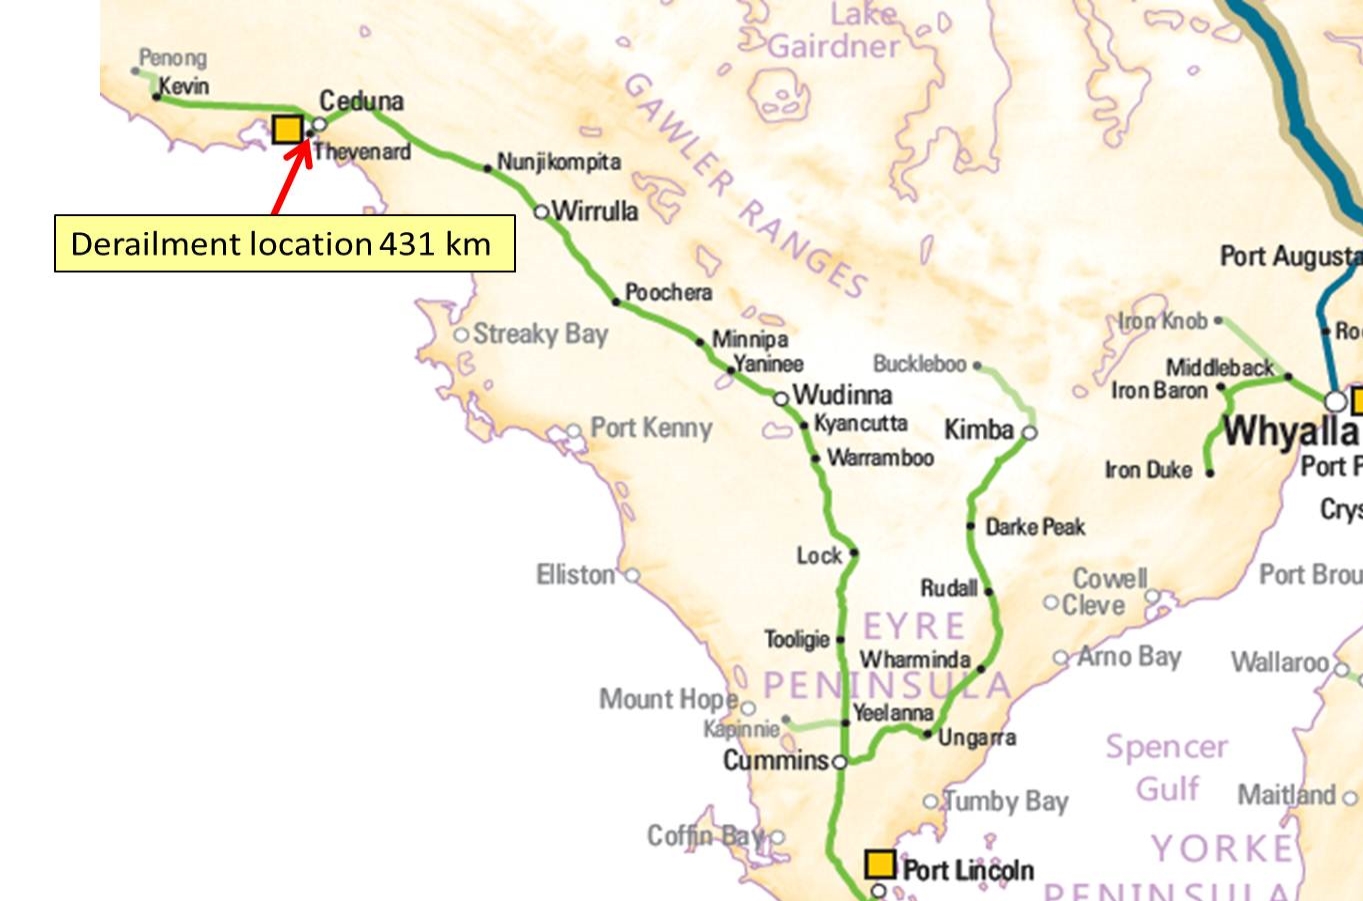
Figure 1: Derailment location map - South Australia
Source: NatMap Railways of Australia annotated by ATSB
At about 0300, the empty train departed Thevenard for the mine, arriving at 0507. After the completion of loading, the train departed the mine at 0636 as train 5DD2.
The Kevin to Thevenard track section had speed restrictions for loaded locomotives; varying from 20km/h to 30km/h due to poor track condition and geometry. As 5DD2 approached Thevenard, the driver increased the train speed to the permitted limit of 30km/h. At about 0906, the driver felt two severe jerks, followed shortly after by a loss of brake pipe air pressure, and then noted an unusual amount of dust rising from the rear of the train. The train was brought to a stop near the 431 km mark[2].
At 0908, the driver contacted train control to advise that the train may have derailed, while the second driver walked back along the train to assess the situation. At 0919 the crew confirmed their location with train control and advised that the rear 13 wagons had derailed.
As the train had derailed and stopped on the approach to the level crossing at Kloeden Street, it caused the level crossing equipment to ring continuously. Consequently, the police attended the site at about 0923.
There were no injuries caused by the derailment, but approximately 120 m of track and 13 wagons were damaged. The track was reinstated for use on 26 October 2014.
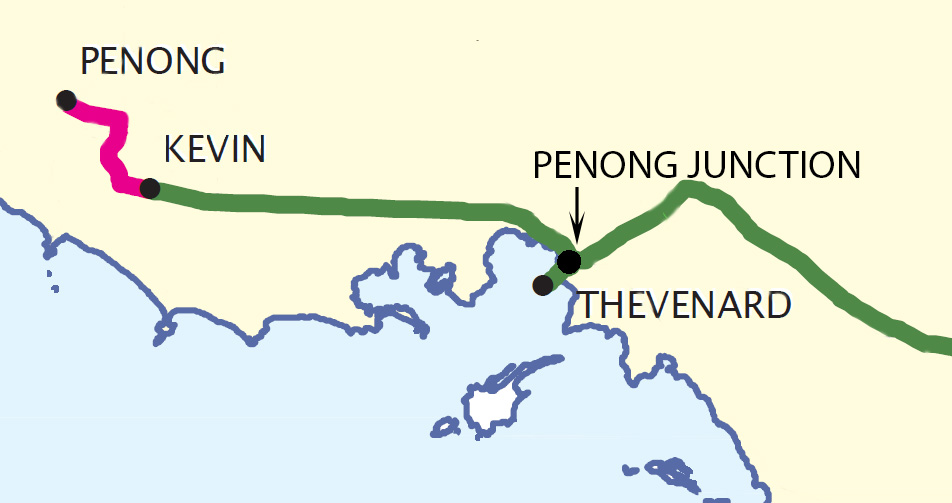
Thevenard is located on the Eyre Peninsula in South Australia, near Ceduna. The rail line extends from Kevin, where a gypsum mine is located, through to Thevenard where the port handles bulk gypsum shipments.
The derailment occurred at the 431.225 km point between Penong Junction and Thevenard (Figure 2).
Figure 2: Map of the Penong – Thevenard track system
Source: South Australian Government, Department for Transport, Energy and Infrastructure, annotated by ATSB
Train and crew information
Train 5DD2 was a gypsum transport service that operated between Kevin and Thevenard. The train consisted of three locomotives (GWA 1601 leading, GWA 873 and GWA 850 trailing) hauling 55 ore hopper wagons of type ENH and ENHA. The train had an overall length of 424 m and a gross weight of 2,475 tonnes. The locomotives were equipped with Quantum event recorders; the information from which was downloaded by GWA and provided to the ATSB for use in the investigation.
ATSB analysis of the information from the train’s recorders indicated that there had been no handling issues experienced during the lead up to the derailment.
As part of the post-derailment investigation, the involved wagons’ wheel profiles were checked by the operator and found to be within serviceable limits.
Train crew
The train was crewed by two drivers; both were appropriately qualified, held the required route certifications and were assessed as fit for duty.
Following the derailment, the drivers underwent mandatory testing for prior drug and alcohol use, with negative results returned for both.
Track Information
History
The Thevenard to Kevin track was a single, narrow gauge[3] railway line from the Port of Thevenard, through Ceduna to the Penong Junction and on to Kevin (Figure 2). The track consisted of a mixture of mechanically-jointed 63 lb/yd (31 kg/m) and 82 lb/yd (41 kg/m) rail, directly fastened to wooden sleepers. The track section where the derailment occurred was constructed in 1915, with the line from the Penong Junction to Kevin being laid in the 1960s. The line was originally operated by South Australian Railways until the mid-1970s, after which it was used by a number of operators. In 1997, a ground lease was granted to Australian Southern Railroad (now GWA). Information available to the ATSB indicated that the general condition of the line had been degrading significantly over a number of years; influenced primarily by limited infrastructure investment and maintenance activity.
The mine at Kevin had been owned and operated by Gypsum Resources Australia since 1984. Penong, located beyond Kevin, had grain storage and loading facilities, but this section of line was closed to rail traffic in 1997 due to minimal use and poor track condition. In a submission to Infrastructure Australia in 2008, the Eyre Regional Development Board identified that significant upgrading and capital investment was required to maintain the rail in an efficient operational state. The investment was not deemed economically justified, unless the gypsum mine could be guaranteed to have continued operations for a number of years.
In 2006, Transfield Services, under contract to GWA, became responsible for the ongoing maintenance and serviceability of the Thevenard to Kevin line. A capital upgrade program was initially proposed for 2013, but the works were further delayed as a commercial agreement with the mine (to ensure continued usage of the rail line) was not yet in place. In July 2014, an agreement was reached with the mine to justify the capital investment needed. A capital works program was then initiated, with a walk-through inspection identifying the scope of the project in August 2014, and capital works scheduled to begin in 2015.
Site observations
Examination of the rail in the area immediately prior to, and at the point of derailment (POD), indicated that the left hand side rail head (in the direction of travel) had fractured near the running face (Figure 3).
Figure 3: Fractured rail head
Source: ATSB and ONRSR
The track showed substantial rail head wear, with evidence of significant metal flow and corrugation (Figure 4). In addition, the wear pattern on the rail face indicated that wheel flanges had been tracking at least 20mm inboard from the rail running face, suggesting lateral (gauge-widening) movement of one or both rails through the POD.
Figure 4: Rail head wear, metal flow and corrugations
Source: ATSB and ONRSR
The combination of substantial head wear and the wheel tracking location increased the likelihood of rail head failure during the passage of a train. From the extent of wear and deformation of the rail head, the lateral movement of the track, and the inboard tracking position of the wheels, the ATSB concluded that the rail had been structurally unable to support the wheel loads, resulting in the vertical collapse and fracturing of the rail head during the passage of train 5DD2.
Given the extent of the rail head wear sustained, and that this type of damage develops progressively over time, it is very likely that the degradation would have been evident during any previous scheduled track inspections.
Inspection and maintenance
Track infrastructure deteriorates over time as a result of usage, age and other factors. It is the infrastructure manager’s role to implement a maintenance regime to ensure the track condition is periodically assessed and returned to an acceptable standard if defects are found. The process is based on a regime of inspection and maintenance aimed at ensuring that the infrastructure condition remains at or above defined limits that are appropriate for the operating requirements of the rail line. It is possible for trains to operate safely on infrastructure that is in a condition below defined limits, provided that appropriate measures are implemented to manage the associated risks.
In this case, the track inspection and maintenance standards were documented in the Westrail Narrow Gauge Mainline Code of Practice (CoP). The CoP specified the monitoring and maintenance requirements, including:
the type of inspections and the frequency required
the documentation requirements after track inspections
acceptable wear limits, and
maintenance requirements for detected defects.
Considering the degraded condition of the Eyre Peninsula rail infrastructure, GWA had issued an addendum to the CoP (dated 1 April 2007), which provided for more frequent inspections, reduced maximum track speeds and modified maintenance defect limits.
Processes
In general, the track maintenance process required identification of track defects through routine inspection, followed by a planning phase to determine the work required and a Work Order being issued to conduct the remediation. To this end, Transfield Services maintained a track fault list; a consolidated list of defects detected during track inspections and the associated rectification work planned. Transfield used this consolidated list to schedule works, and it was the only documentation provided to GWA for their oversight of the state of the track.
Track gauge
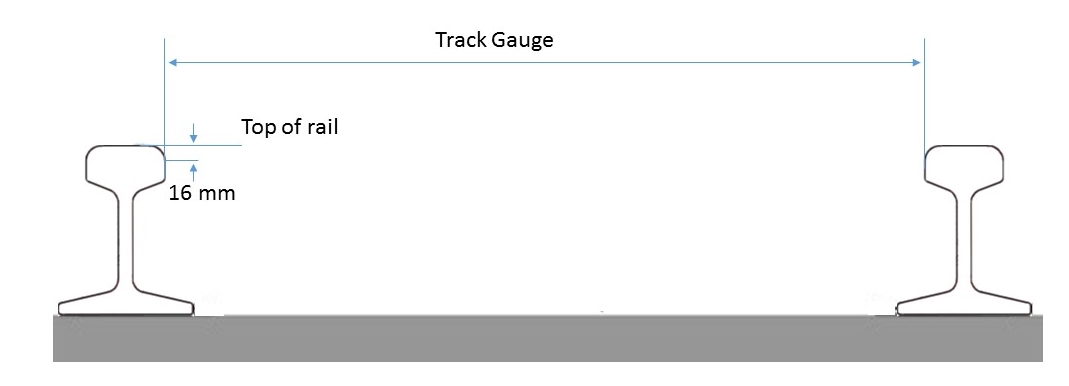
Track gauge is the distance between the gauge faces of the two rails and is normally measured at a point 16 mm below the top of the rail head (Figure 5). In this case, the rail head was so worn and distorted that track gauge could not be effectively measured in this manner during post-derailment inspections. Considering the evident running position of the rail wheels however, (Figure 6), the track gauge had very likely exceeded the maximum limit documented in the CoP addendum.
Figure 5: Track gauge measurement point
Figure 6: Rail condition and running position of wheels
Source: ATSB and ONRSR
The condition of sleepers and fasteners is critical for maintaining track gauge. In this case, their condition would have been difficult to determine visually, due to extensive coverage by gypsum product (Figure 7). Post-derailment examination however, found that the sleepers were in a poor condition, with limited gauge-holding capacity at the point of derailment. While the period over which gauge widening and poor sleeper/fastener condition had developed was unable to be determined, the level of rail wear and sleeper condition suggested that the track had been operating in a degraded condition for some time.
Rail condition
The CoP required rail head wear to be periodically assessed against prescribed limits, with defects beyond those limits reported for remedial action. Documentation is required detailing the location and wear levels where top or combined wear to the head profile exceeds 20% and side wear is greater than 15%. Where the prescribed wear limits are exceeded, a rating of the rail may be carried out using procedures detailed in the CoP, taking into account local factors and any pre-existing speed restrictions.
Corrugation of the rail was also evident at the point of derailment – a defect which develops over time and can lead to failure of the rail if left untreated. It was evident that this condition had been present for some time and would likely have been visible during scheduled track inspections.
During the investigation, the ATSB was unable to identify any documented evidence that the level of rail head wear or corrugation in the area of the derailment was being monitored, or that the severity of the condition/s had been reported to GWA for reassessment of operating limitations (load rating and speed restrictions).
Figure 7: Complete product coverage of sleepers and fasteners
Source: ATSB and ONRSR
Track inspection
The documentation suite in use for track inspection outlined the requirements for patrol, general and detailed inspections; all of which were used in conjunction with Transfield’s Technical Maintenance Plan to meet the CoP requirements. These documents detailed the procedures for completing the different types of inspections on various rail infrastructure elements, and contained inspection worksheets to record details of completed inspections and corrective work performed.
At the time of the derailment, the minimum (baseline) inspection requirements prescribed by the CoP addendum were for a scheduled track patrol to be conducted every 48 hours, a track geometry car to be run at a minimum of once a year, and on-rail ultrasonic testing required every 8 years.
While the CoP addendum procedures required 48-hourly inspections, there were no records available to confirm that those inspections had taken place between June 2014 and the derailment in October. Records were also unable to establish when the last track geometry car was run to detect and quantify any rail head defects. The track geometry car had the capability of detecting wide track gauge as well as the extent of the rail head wear.
Records provided to the investigation showed that the most recent ultrasonic testing was conducted in 2006, with no defects noted at the point of derailment at that time. The next ultrasonic test was due in 2014, however an earlier decision had been made, in light of the upgrade work proposed in 2013, to run that test during the early stages of the upgrade program.
Track maintenance
The risks presented by the deteriorating track infrastructure were able to be managed in accordance with the CoP and addendum, by applying operational restrictions and increasing the inspection frequency. The temporary speed restrictions in force at the point of derailment were applied in 2009, when Transfield Services was first contracted to provide track maintenance services.
The CoP indicated that speed restrictions, when used in conjunction with increased inspection frequency, were an appropriate risk control for some isolated defects until such time as the defects were rectified or a plan for a strategic upgrade was in place. While temporary speed restrictions can reduce the likelihood and consequences of an incident involving degraded track, they were not intended to be used as long term measures for ensuring the safety of the line.
At the time of the occurrence, other sections of the Eyre Peninsula rail infrastructure had been either closed due to the condition of the track, or had current speed restrictions, with the maximum line speed for a loaded train of 30 km/h. All of the speed restrictions current at the time of the derailment had been applied as a response to the state of the infrastructure.
Related occurrence
Derailment at Charra, November 2 2014
At about 1800 hours on 2 November 2014, train 1DD5 derailed at the 473.938 km mark between Kevin and the Penong junction. Subsequent investigation found a 200 mm section of broken rail associated with a mechanical joint. It was concluded that the broken section had separated during the passage of 1DD5 (Figure 8).
Figure 8: Rail defect in mechanical joint
Source: Transfield Services
While records of the inspections conducted after June 2014 were unavailable, the evidence of forced surface contact across the fractured web suggested the fracture within the mechanical joint had likely been present for a period longer than the time between inspections.
Investigations at the time found no records of routine inspections taking place at a frequency that would have detected the broken rail prior to the passage of the train. Similarly, there were no indications that a potential issue was being monitored and maintained appropriately, or had been reported to the rail operator.
On the basis of the evidence available from the incident site, it was concluded that the derailment of train 5DD2 resulted from the combined effects of a substantially worn rail head profile and wide track gauge. These conditions are characteristic of aging and deteriorating infrastructure. To properly manage a deteriorating asset, GWA, as the rail transport operator (RTO), was responsible for ensuring the standards being applied were appropriate for safe rail operations. This required an appropriate level of oversight of the contracted maintenance provider. As that provider, Transfield Services was required to periodically inspect, record and report the condition of the track to GWA, so that appropriate assessments and decisions could be made in managing the track condition.
Documentation and reporting
The ATSB found no evidence to indicate that regular (visual) defect monitoring and reporting was being conducted as specified in the CoP. As a result, remedial maintenance actions were not being planned or implemented. Records of routine inspections were not being kept, and accordingly, there was no information indicating the condition of the rail at the point of derailment. Without defects being recorded and entered into the maintenance scheduling system, no monitoring or maintenance actions were being implemented. Similarly, without the appropriate documentation and reporting, it was likely that GWA was not fully aware of the deteriorated state of the rail and the potential requirement for immediate maintenance actions.
In a similar manner, it was also evident that the track geometry inspection car was not being run at the required intervals. Use of the track geometry car may have identified any track alignment, wide gauge or rail head wear defects that required immediate action and which may not have been noted by visual (hi-rail) running inspections.
The track fault list examined by the ATSB did not include monitored defects, and had no entries between June 2014 and the incident – suggesting that known defects were not being monitored and new defects were not being identified and added to the list.
There was physical evidence to suggest that the defects which contributed to the derailment had been present for a significant period of time – further indicating that the inspection regime was not capturing defects or monitoring them appropriately. The nature of the track defects present at the derailment site (substantial rail head wear, wide gauge and corrugation) was such that they should have been identifiable during routine inspections, and consequently, should have been subject to a monitoring regime as defined within the CoP.
Oversight
The application of temporary speed restrictions in 2009, coupled with an increase in the inspection frequency of the track at the point of derailment suggested that from this time, there was at least a broad level of understanding around the deteriorated state of the track. The CoP indicated that speed restrictions and increased inspection frequency was an acceptable minimum response when applied to isolated defects, however it also indicated that a more comprehensive response may be necessary where multiple defects exist in a localised area. GWA had identified that a major upgrade was required to address the cumulative risks, but the implementation of this had been delayed due to ongoing commercial negotiations with the mine operator.
Whilst Transfield cited track occupancy authorities and daily work diaries as evidence that track inspections had occurred, there were no specific inspection records, nor were there any reports of defects found or maintenance action taken following these regular inspections. GWA had not required the routine provision of inspection records, with the only documentation received for oversight of the track condition being a consolidated track fault list provided quarterly. The track fault list contained no defects found or rectification work conducted as a result of routine inspections between June 2014 and the incident. The level of detail contained in the fault list was not sufficient to fully convey the deteriorated state of the track, and defects that required on-going monitoring were not included in the list. As such, GWA was likely not fully aware of the true state of the track infrastructure.
Where the rail was known to be in poor condition, GWA had not maintained sufficient oversight in managing the activities of the infrastructure maintainer. The limited information requested from, or provided by the contracted maintenance provider resulted in GWA being unable to effectively manage the deteriorating condition of the track. This led to the track remaining in operation while it deteriorated to a level below the limits documented in the CoP and addendum, and without having undergone a process of standards reassessment to ensure that ongoing rail operations remained safe.
Findings
From the evidence available, the following findings are made with respect to the derailment of train 5DD2 at Ceduna, South Australia, on 23 October 2014. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Safety issues, or system problems, are highlighted in bold to emphasise their importance. A safety issue is an event or condition that increases safety risk and (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
Contributing factors
The track infrastructure between Penong and Thevenard, SA had progressively degraded and was generally in poor condition.
Substantial rail head wear and corrugation in the vicinity of the derailment, combined with a wide gauge condition and the consequent wheel tracking away from the rail web led to localised rail head failure and the derailment of train 5DD2.
Track defect monitoring and reporting was not being conducted as specified in theWestrail Narrow Gauge Mainline Code of Practice, limiting the awareness of the deteriorating track condition and the need for reassessment of track operating limits. [Safety issue]
The rail transport operator (GWA) had not maintained sufficient oversight of the activities of the rail infrastructure manager (Transfield Services), allowing the track to deteriorate to a level where trains could not be reliably run in a safe manner. [Safety Issue]
Safety issues and actions
The safety issues identified during this investigation are listed in the Findings and Safety issues and actions sections of this report. The Australian Transport Safety Bureau (ATSB) expects that all safety issues identified by the investigation should be addressed by the relevant organisation(s). In addressing those issues, the ATSB prefers to encourage relevant organisation(s) to proactively initiate safety action, rather than to issue formal safety recommendations or safety advisory notices.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Where relevant, safety issues and actions will be updated on the ATSB website as information comes to hand. The initial public version of these safety issues and actions are in PDF on the ATSB website.
Maintenance, defect monitoring and reporting as per CoP
Track defect monitoring and reporting was not being conducted as specified in the Westrail Narrow Gauge Mainline Code of Practice, limiting the awareness of the deteriorating track condition and the need for reassessment of track operating limits.
The rail transport operator (GWA) had not maintained sufficient oversight of the activities of the rail infrastructure manager (Transfield Services), allowing the track to deteriorate to a level where trains could not be reliably run in a safe manner.
The sources of information during the investigation included:
Genesee & Wyoming Australia
Transfield Services Ltd
Office of the National Rail Safety Regulator
References
Rail Industry Safety and Standards Board (2010), Glossary of Rail Terminology – Guideline. Available from: www.rissb.com.au
AS 1085.1 - Railway track material—Steel rails—History (Supplement 1 to AS 1085.1—2002).
Westrail Narrow Gauge Mainline Code of Practice Version Draft 1998
Addendum to the Westnet Rail Narrow Gauge Mainline Code of Practice for the Eyre Peninsula Railroad
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Genesee & Wyoming Australia, Transfield Services, the Office of the National Rail Safety Regulator (ONRSR) and the crew of train 5DD2.
Submissions were received from Genesee & Wyoming Australia and the Office of the National Rail Safety Regulator (ONRSR). The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
The pilot reported that the aircraft was departing empty from the Snake Creek Fish Farm after delivering a load of freight. The main fuel tanks were 3/4 full and the auxiliary tanks were full.
After the aircraft speed had passed Vmca and the aircraft was becoming airborne, the right engine failed. The pilot closed the throttles, selected the right propeller to feather, landed the aircraft and commenced braking. He assessed that insufficient runway remained for a successful stop, so he initiated a ground loop to the left. Just before the aircraft stopped, the nose leg struck a mound of earth that had been hidden in the grass. This caused the nose gear leg to collapse, and both propellers were damaged.
No reason for the engine failure could be established. The grass on the airstrip was long. This may have resulted in lower acceleration performance than the pilot had anticipated.
The aircraft was engaged on a VFR pilot navigation training flight. One cadet pilot had flown the aircraft from Tamworth to Coolangatta via Coffs Harbour earlier in the day. A second cadet pilot was conducting the return leg to Tamworth, with a landing at Glen Innes, under the supervision of an instructor.
At about 80 feet after take-off from Glen Innes the instructor initiated a practice engine failure. The aircraft was about 10 knots below the glide speed for the flap setting in use at this point. The cadet pilot promptly lowered the nose, but not sufficiently to obtain the desired glide speed or maintain the take-off speed. The instructor pushed the controls forward to lower the nose to the attitude normally required to maintain a safe speed. The flap setting was not altered to a landing position. Shortly after this the instructor realised that a high sink rate had developed and took corrective action to reduce the sink rate, including the application of power. The sink rate could not be arrested in the distance available and the aircraft landed very heavily.
Both main landing gears were damaged, and the right wing was rotated nose down. The aircraft came to rest on the runway, after a ground run of 100 metres. The cadet pilot suffered a cut above his left eye when his head struck the transmit switch on the control yoke during the landing impact.
The company's operations manual for the aircraft type specifies that practice engine failures may be conducted at a minimum altitude of 500 feet above the aerodrome, and that the ensuing approach must be terminated at a minimum height of 200 feet. An obstacle clearance climb is to be terminated at 300 feet above the aerodrome and a normal climb profile adopted. The operator considers that a practice engine failure during an obstacle clearance climb phase is unsafe and does not include such a training exercise. In addition, with a temperature of 22 deg C, the density altitude of 4783 feet could be expected to exacerbate the problems.
Factors
A high-density altitude prevailed.
The instructor initiated a training manoeuvre at a height and speed from which recovery was difficult.
The optimum aircraft configuration was not adopted during the power-off approach.
Visual approaches to Sydney Airport were in progress, domestic arrivals being processed for runway 34R, and international arrivals for runway 34L. The arrival sequence was being handled by Approach South (APP-S) and Approach North (APP-N) radar controllers. Traffic density was described as light to medium.
To resolve a traffic management problem in his airspace, APP-S coordinated with APP-N for a Metro 23 to complete a right circuit for arrival to runway 34R. This involved radar vectoring the aircraft to pass overhead Sydney Airport onto a right downwind leg, east of the runway complex, an area which was normally under the jurisdiction of APP-N. However, as there was no traffic east of the runway at the time, it was agreed to keep the Metro 23 on the APP-S frequency.
A SAAB 340 (SF34) was also being processed by APP-S for a landing on runway 34R and was given radar vectors to join on left downwind. During the arrival sequence, the crews of both aircraft were given instructions to descend to 2,000 ft and were vectored onto opposing headings for their respective base legs. Some coordination concerning other aircraft took place at about this time. When the Metro 23 was passing through the final approach path of runway 34R, the crew questioned the controller as to whether they were to turn the aircraft right to intercept final approach. APP-S confirmed this, then vectored the SF34 to remain clear of the Metro 23. Recorded radar data indicated the aircraft passed within 2 NM of each other, with a minimum vertical separation of 200 ft. The required radar separation standard was 3 NM laterally or 1,000 ft vertically.
The decision to leave the Metro 23 on the APP-S frequency, whilst being vectored within APP-N, airspace was considered to be a significant factor in the development of this occurrence. Whilst the APP-S controller believed he had not forgotten to issue the crew of the Metro 23 with a clearance to turn onto final approach, it appeared he had a mind-set, or expectancy, that APP-N would process the aircraft, as would normally happen. This mind-set was experienced despite the fact that the colour of the Metro 23's radar symbol indicated it was under the jurisdiction of APP-S.
The student pilot was making an approach for a normal landing. During the landing flare he raised the nose too high, and the aircraft ballooned. The student attempted to correct the situation by adding power and lowering the nose. The aircraft was no longer aligned with the runway and the student used the rudder to turn the aircraft. As he was completing this action the stall warning sounded. The student opened the throttle to full power, to go around, but he did not stop the aircraft from pitching more nose-up nor did he centralise the rudders. The aircraft stalled, pitched nose down and rolled to the left. The left wing and propeller struck the ground before the student could take any further action. The student turned the magneto and power switches off before leaving the wreckage.
The student's inexperience was the major factor in his misjudgement of the approach and his use of incorrect recovery action.
Whilst being hover taxied between hangars, in strong gusty wind conditions, the helicopter rotated rapidly to the right, struck the ground, and rolled onto its side. Both occupants were able to evacuate the machine without injury. The instructor pilot reported that the helicopter was being flown by the student pilot at the time.
With the wind gusting from the south, the aircraft was lifted into the hover on an easterly heading, then rotated to the right through 180 degrees. As it approached a westerly heading it swung rapidly to the right. Full left pedal and power reduction failed to arrest the rotation which continued for two or three turns before the helicopter struck the ground and rolled onto its side.
No mechanical defects were reported that may have contributed to the accident. It was the opinion of both the instructor pilot, and the operator's chief pilot, that the accident was consistent with the loss of tail rotor authority.