The incident occurred just prior to official first light, during a shift change in both the control tower and the departure/arrivals centre and during a busy period.
During multiple departurers in suitable weather conditions, the aerodrome controller is required to retain the aircraft on tower frequency and provide positive visual separation (diverging tracks) until the aircraft are handed off to the departure controller.
VH-FWJ and VH-MLX were departing, in turn, from runway 21 on the Perth to Ballidu track. Departure instructions were given to the aircraft which would allow them an unrestricted climb on headings 30 degrees apart (VH-FWJ on 360 degrees and VH-MLX on 030 degrees). When the departure controller passed the instructions to the aerodrome controller for relay to the aircraft, the aerodrome controller was reminded that he would be responsible for visual separation. However, the controller forgot to instruct the aircraft to remain on the tower frequency.
Both aircraft transferred to departure frequency shortly after take-off. VH-FWJ commenced its turn on to 360 degrees as it passed through 1000 feet, 4 nautical miles from take-off. VH-MLX (with a better climb performance than VH-FWJ) commenced its turn on to 030 degrees as it passed through 1000 feet 2 nautical miles from take-off. The resultant tracks placed the aircraft in potential conflict.
Although the potential conflict was recognised by both the aerodrome controller and the departure controller, corrective instructions had to be passed to the aircraft by the departure controller, resulting in a short delay between when the potential conflict was identified and the aircraft were able to respond. As a result the radar returns came within half a nautical mile horizontally and less than 200 feet vertically. Although the two radar returns appeared to be very close together, the aircraft were observed to be visually apart at all times.
The investigation disclosed that although the traffic load was normal for that time of the day it was significant enough to prevent a comprehensive shift change briefing from being carried out in the tower. Evidence also indicated that the aerodrome controller was distracted by the activity associated with the shift change and this plus the combination of low external light conditions and high workload led to temporary task saturation. Consequently the aerodrome controller did not complete his assigned tasks nor did he register the reminder given by the departure controller.
SIGNIFICANT FACTORS
The following factors were considered relevant to the development of the occurrence:
1. The aerodrome controller was distracted from his assigned tasks by the shift change which occurred during a time of high workload and less than optimum light conditions.
2. The aircraft had significantly different climb performance, with the climb profile of VH-FWJ being about half that of VH-MLX.
3. The provision of positive separation instructions from the tower was made difficult because the aircraft were not on the tower frequency. The delay associated with the provision of this information by the departure controller, although not excessive, was sufficient for the conflict to occur.
SAFETY ACTION
The following safety enhancement action was taken after the occurrence.
1. The Civil Aviation Authority reminded relevant Perth staff of the requirements for the application of visual separation during departure.
2. The Civil Aviation Authority took action to rearrange the tower shift change over so that it occurs prior to the known busy period which starts around 0600.
The aircraft was flying over the Grampians Mountain ranges, the highest peak of which is nearly 4000 feet. The pilot reported that he had diverted slightly to the north of track to avoid the higher peaks of the first range but also to keep clear of a storm to the south and to keep below cloud. As the flight proceeded, the pilot realised that the aircraft was not going to clear the rising ground. He attempted to turn away from the rising ground but realised that the aircraft was going to sink into the trees in the heavily timbered terrain. The pilot lowered flap and stalled the aircraft into the tops of the trees, estimated to be between 20 and 30 metres high.
The aircraft was destroyed as it fell through the trees to the ground. The two occupants spent the night at the site. Early the next morning, when there was no longer any sign or smell of fuel, they turned the radio on and made a call to Melbourne, after which search and rescue procedures were commenced.
The pilot initially believed that the engine had suffered some form of power loss. The wreckage was inspected by an aircraft engineer who reported that damage to the propeller was consistent with the engine delivering significant power at the time of propeller impact. The Bureau of Meteorology advised that there were active thunderstorms in the area at the time with the possibility of severe downdrafts. In addition, conditions were conducive to the formation of carburettor ice. However, an eyewitness reported that the wind was calm, and the sky was clear at the time of the accident.
The accident was not formally investigated by the Bureau, and it was therefore not possible to determine significant factors that could be supported by sound evidence.
Shortly after lift-off, at about 50 feet, the right engine surged and lost power. The pilot was unable to control the yawing effect and attempted a landing beyond the departure end of the airstrip. During this attempt the engine surged to power once but as this exacerbated his control difficulties the pilot closed both throttles. The aircraft cartwheeled after striking the ground with the left wingtip. The aircraft came to rest in a paddock beyond the 1,000 metre airstrip.
The fuel selector for the right engine was found in the auxiliary position. The pilot later commented that he probably missed the fuel selection out of his pre-take-off checklist. He said that he had been in the habit of using a memorised checklist for the operation of the aircraft and at times he had forgotten to switch the tank selection from auxiliary to main tank prior to landing, as required by the operating instructions in the aircraft flight manual. The pilot also commented that he felt uncurrent in asymmetric operations.
Examination of the right engine did not reveal any defects which could cause a power loss.
Significant Factors
The following factors were considered relevant to the development of the accident:
1. The pilot did not follow flight manual operating instructions for the operation of the aircraft fuel system.
2. The pilot relied on a memorised checklist.
3. The pilot was uncurrent in asymmetric operations.
On selecting gear down, there was no green light indication in the cockpit and the landing gear motor continued to operate. The pilot noticed that both main gears were trailing. He was unable to retract or extend the landing gear by either the normal or emergency extension systems. The aircraft was landed in this configuration.
Investigation found that the retaining circlip in the hydraulic ram for the left main landing gear door had failed. This allowed the actuating ram to separate from its housing and seal, causing the loss of all hydraulic oil from the landing gear reservoir.
The cause for the circlip failure could not be determined.
Shortly after commencing the take-off the aircraft made an uncommanded turn to the right and ran off the sealed runway. Before the aircraft could be brought to a stop the left propeller was damaged as it struck a T-VASIS box.
The crew had deactivated the nosewheel steering system during the early portion of the take-off, in accordance with standard operating procedures. An extensive investigation by the operator and manufacturer did not disclose the cause of the uncommanded turn.
The manufacturer recommended, and the operator has adopted, a modified procedure aimed at avoiding a repetition of this incident.
The student pilot was sent solo to conduct a sortie of normal and flapless circuits. After an uneventful first circuit, the pilot landed nose first on the second circuit and, after four bounces, the wheel separated from the nose leg.
The pilot had extended slightly on downwind to allow for aircraft ahead in the traffic pattern. As a result, the final leg was flown lower and faster than normal, and the pilot evidently misjudged the flare. She was not able to recover from the ensuing bounces before the nosewheel was dislodged.
On 15 July 2015, a Cessna 210L aircraft, registered VH-TCI (TCI), was inbound to Broome Airport from Cockatoo Island, Western Australia. The pilot was the only person on board. At about 1037 Western Standard Time (WST), when the aircraft was about 40 NM from Broome, the pilot made an inbound call on the Broome air traffic control (ATC) Tower frequency. The Tower controller was unable to hear what the pilot said, and responded by broadcasting that the calling aircraft was transmitting a carrier wave only, with no voice modulation.[1] Even though there appeared to be a problem with radio transmissions, the pilot could hear the Tower controller and the pilots of other aircraft communicating on the frequency.
The pilot checked the aircraft radio equipment, but was unable to identify any faults. They tried using another radio and calling the pilots of other aircraft, but were still unable to establish twoway communications. The pilot set the transponder code to indicate a loss of two-way communications,[2] and established the aircraft in a holding pattern to the north of Broome, just outside Broome Class D airspace.[3] The pilot stated the holding pattern was between 25 and 27 NM (remaining outside 25 NM, then turning inbound in the pattern at 27 NM) from Broome and at an altitude of about 5,000 ft. The pilot continued to try to establish contact with the Tower controller and other aircraft in the area without success.
Without having been able to establish two-way communications via radio, the pilot used a mobile telephone to contact the operator, who provided a telephone number for Broome Tower. The pilot subsequently discovered that the number was incorrect, so asked the operator to search for the correct number.
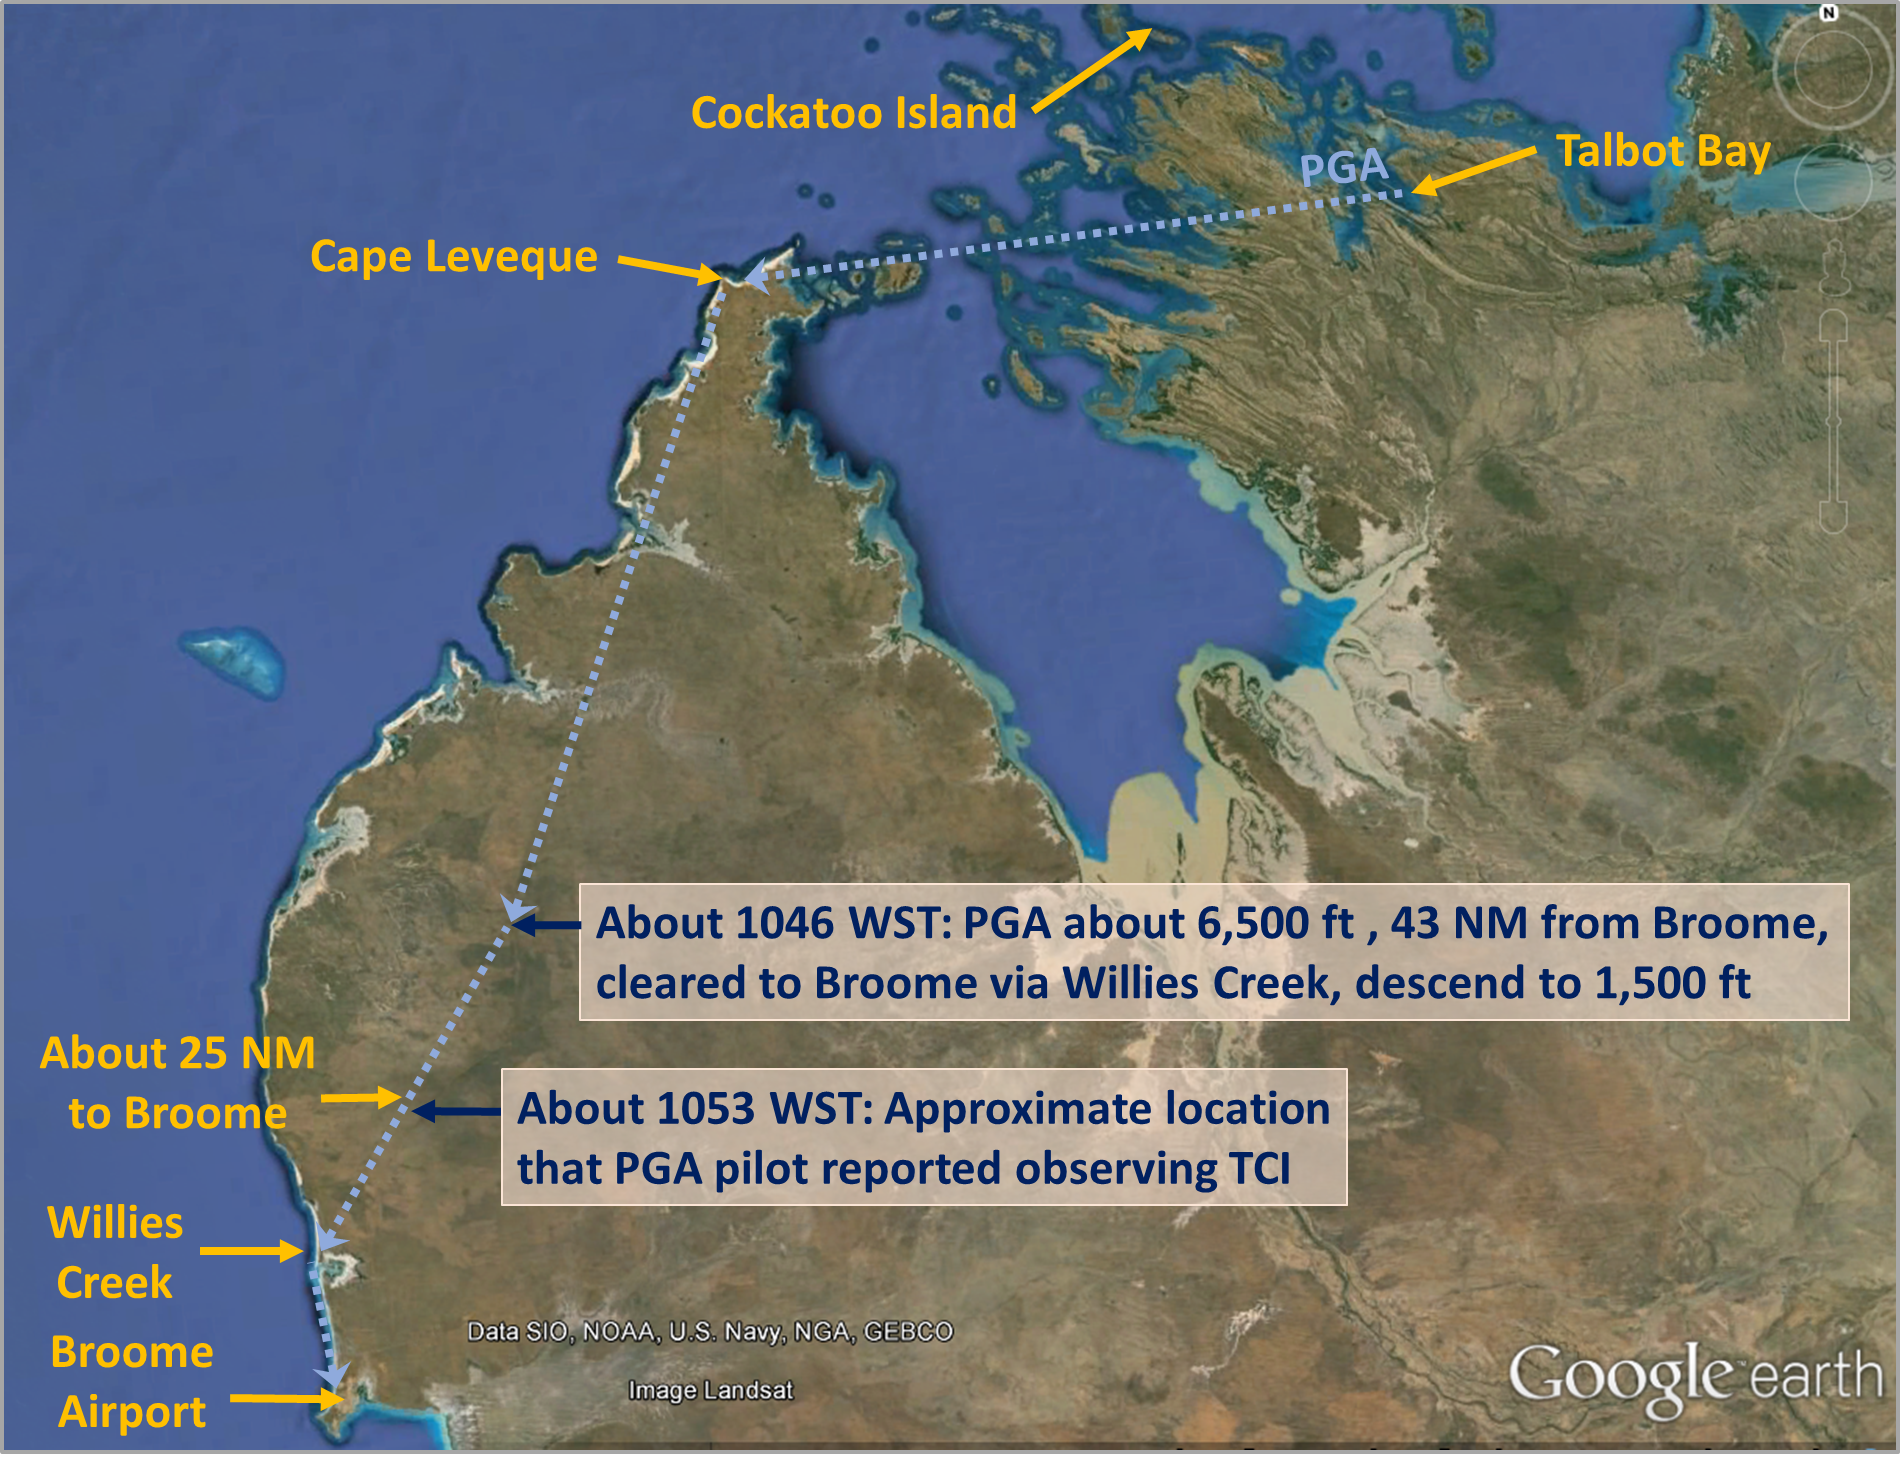
At about 1046 (about 9 minutes after the pilot of TCI reported making an inbound call that was only transmitting a carrier wave) the pilot of a Cessna 208, VHPGA (PGA) made an inbound call on the Broome Tower frequency. At that time, the aircraft was about 43 NM from Broome, on the 021° bearing (from the Broome non-directional beacon). PGA was inbound to Broome at about 6,500 ft after conducting a scenic flight, having departed Talbot Bay for Broome via Cape Leveque and Willies Creek (Figure 1). On board were the pilot and 12 passengers. The Tower controller acknowledged the call and cleared PGA to enter controlled airspace (Class D airspace), tracking to Broome via Willies Creek, and descending to 1,500 ft.
Figure 1: Map showing the location of Cockatoo Island where TCI departed for Broome and the location of Talbot Bay where PGA departed for Broome via Cape Leveque and Willies Creek (blue track). Map also shows the approximate location of PGA from the aircraft’s real-time satellite tracking system as provided by the operator.
Source: Google earth, modified by the ATSB.
At about 1053, the pilot of PGA heard the aircraft’s traffic information system[4] alert ‘traffic 12 o’clock[5] same level’ (or similar words), indicating that an aircraft (subsequently identified as TCI) was directly ahead of PGA, at the same altitude, and within 0.25 NM. The pilot of PGA sighted the aircraft (subsequently identified as TCI) and observed it flying in the opposite direction on the right side, in close proximity. At about the same time, the pilot of TCI recalled that an aircraft (later identified as PGA) was seen to fly overhead.
After the aircraft had passed each other, the pilot of PGA advised the Tower controller that an aircraft had ‘passed at 26 miles through 5,000 same level looked like a 210.’ The Tower controller was subsequently able to establish limited one-way communication with the pilot of TCI (who was still unable to transmit voice communication), asking for confirmation of intentions, and using two short clicks/transmissions to acknowledge receipt of the Tower controller’s transmissions. The Tower controller then broadcast a telephone number for the pilot, and asked the pilot to make contact on that number if possible.
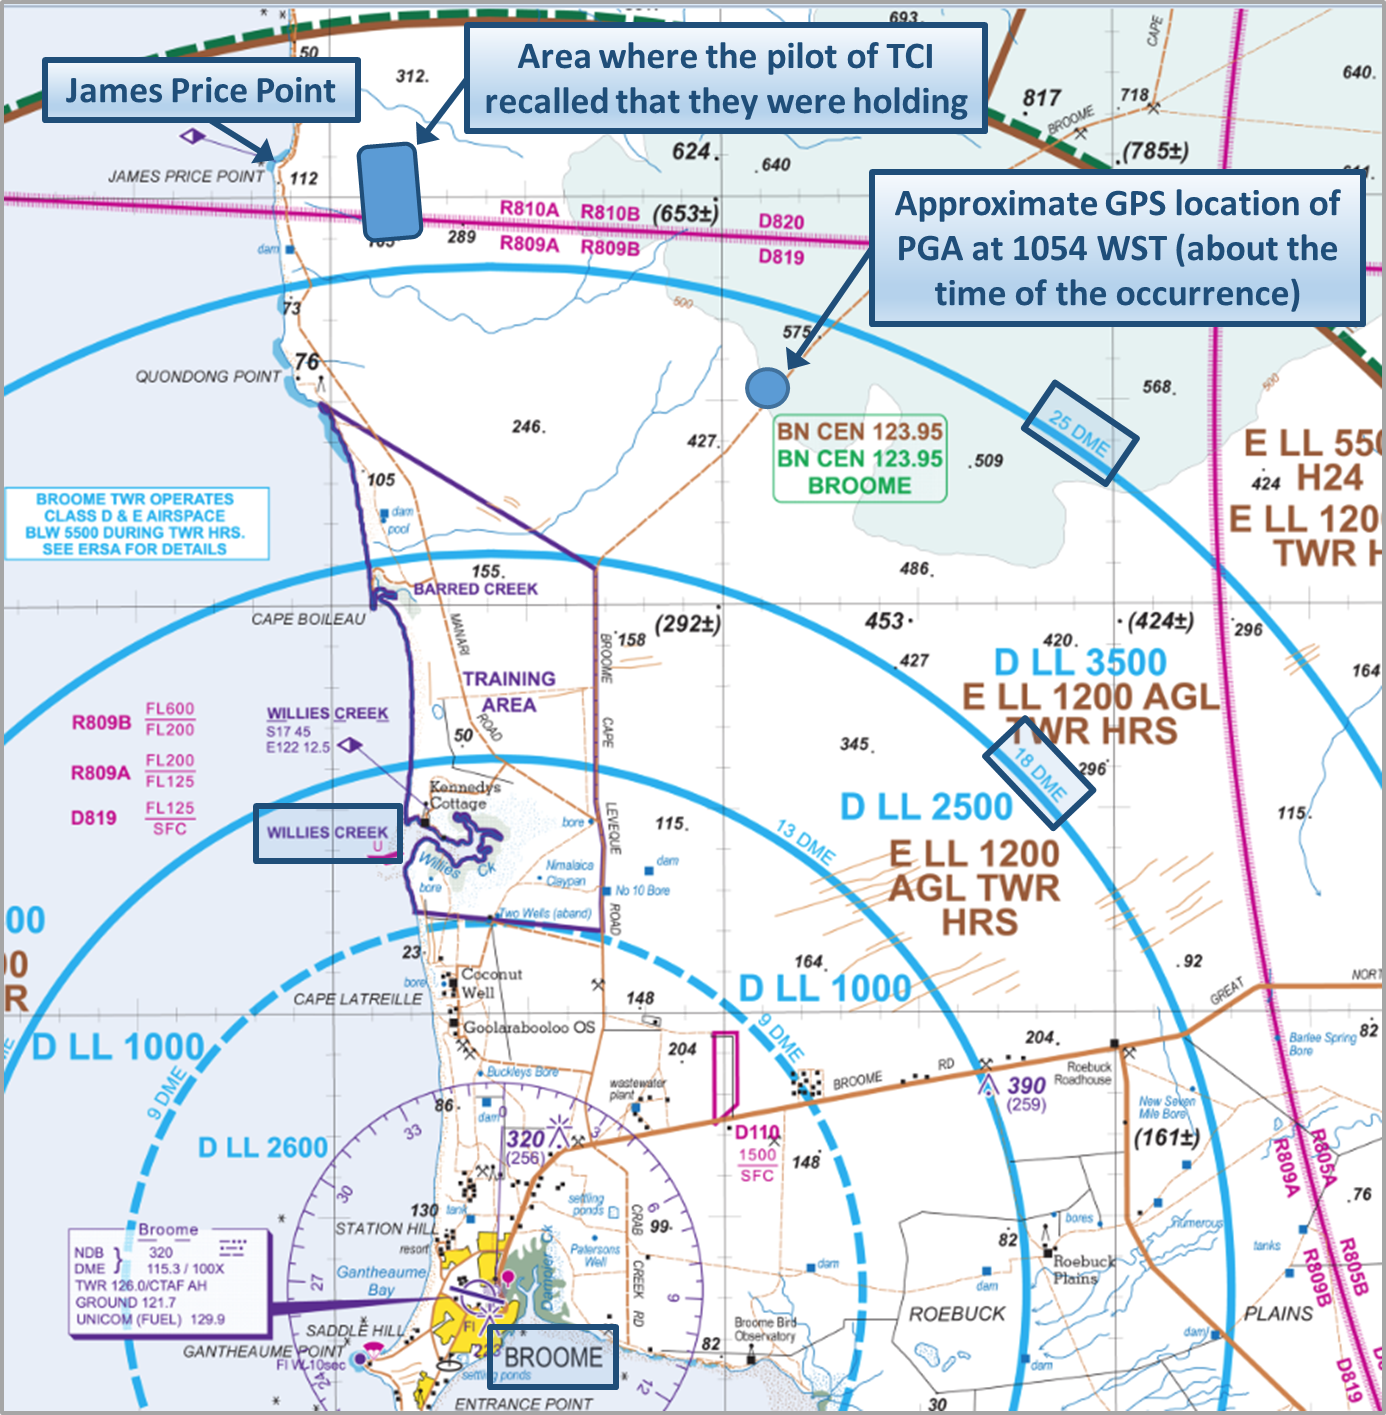
Note: The pilot of TCI recalled holding over land, near James Price Point, outside of Class D airspace. Communications between ATC and the pilot of PGA immediately following the point at which the aircraft passed, suggested that the incident occurred further to the east, at about 26 NM from Broome. A later communication between ATC and the pilot of PGA suggested that the incident occurred about 23 NM from Broome. Information provided to the ATSB by the pilot for the incident flight from the tracking data from PGA’s real-time satellite tracking system also suggested that the incident occurred near the latter location (Figure 2).
Figure 2: Broome Visual Terminal Chart depicting the area where the pilot of each aircraft believed they were located at the time of the occurrence.
Source: Airservices Australia, modified by the ATSB
The pilot of TCI contacted the Tower controller by telephone on the number provided, and was cleared to follow PGA to Broome, via Willies Creek. They also agreed to make a long transmission when TCI was 10 NM from Broome, and to ‘transmit blind’[6] beyond that point. The controller then advised the pilot of PGA of the aircraft TCI, a Cessna 210, and advised that TCI would track inbound to Broome behind PGA. The pilot of PGA acknowledged this information.
At about 1103, the Tower controller cleared TCI for a visual approach as number two to land, and asked the pilot to make ‘one click on left base’. The pilot of TCI acknowledged the controller with two short clicks/transmissions. PGA landed ahead of TCI at about 1104. About 3 minutes later, the pilot of TCI made a short click/transmission on the Tower frequency to indicate that they were on left base. The Tower controller responded by acknowledging that TCI was ‘transmitting blind’, and cleared TCI to land. TCI landed without further incident.
Radio failure
After the event, the operator investigated the reason for the radio failure in TCI. They found that an electrical cable for the microphone plug had come loose, resulting in the failure of that part of the communication system.
Pilot of TCI comment
The pilot of TCI reported that when they detected the radio failure, they were on descent from 8,000 ft. The pilot elected to hold at 5,000 ft outside Class D airspace, to remain clear of aircraft operating at 4,500 ft and 5,500 ft,[7] and to enable mobile telephone reception (to contact the operator and air traffic control).
The pilot of TCI reported hearing the pilot of PGA make an inbound call, and was monitoring the position of PGA using an application on an iPad. The pilot commented that although the iPad application did not provide real-time information, and that the accuracy of the information was limited, it nonetheless provided general information about aircraft in the vicinity. Based upon their understanding of the circumstances, the pilot believed that there was some distance between the area in which they were holding and the planned track of PGA.
Having identified that there was a communication problem, the pilot consulted the En Route Supplement Australia (ERSA), but considered the guidance available in that document to be of limited relevance under the circumstances.
When the two aircraft crossed, the pilot of TCI believed that PGA was about 500 ft above and about 1 NM (1.9 km) horizontally separated, at the closest point.
Pilot of PGA comment
The pilot of PGA reported that they had been maintaining a listening watch on the Broome Tower frequency from about 65 NM out, to gain situational awareness of the traffic operating in the area. The pilot heard the Broome Tower controller broadcast that an aircraft was only transmitting carrier wave, with no voice modulation.
The pilot estimated at the closest point when passing, TCI was about 50 m (0.03 NM) horizontally separated from PGA, and slightly below. After landing, the pilot indicated that several of the passengers made comments regarding the other aircraft (TCI).
The pilot obtained the tracking data from PGA’s real-time satellite tracking system for the flight that showed the location of PGA at the time of the occurrence. That location is consistent with the approximate location, as shown in Figure 2, that the pilot of PGA observed TCI.
Based upon their experience flying in the Broome area, the pilot strongly believed radar facilities should be available to assist with management of the large volume of diverse air traffic that operates at Broome.
Safety message
This occurrence highlights the fundamental importance of communication – where the quality of communication is compromised for any reason, an effective pilot lookout becomes increasingly important. Awareness of the limitations of the see-and-avoid principle may assist pilots in developing effective lookout techniques. The ATSB publication Limitations of the See-and-Avoid Principle provides information on the limitations of seeing and avoiding another aircraft and measures that can be taken to increase the chance of sighting other traffic. The Civil Aviation Safety Authority (CASA) publication CAAP 166-2(1) Pilots’ responsibility for collision avoidance in the vicinity of non-controlled aerodromes using ‘see-and-avoid’ also contains information on measures that can be taken to increase the chance of sighting other traffic.
Communication difficulties can generate a high workload and stressful environment for all concerned, and have the potential to escalate into a more serious situation if not handled effectively. Pilots are encouraged to familiarise themselves with the actions outlined in the ERSA, that may be appropriate when dealing with communication difficulties. Although in this case, the pilot considered the guidance to be of limited relevance, the information may be important in guiding pilot decision making under other circumstances. A common understanding between air traffic control and pilots experiencing radio difficulties, with regard to the intended actions of the pilot, may be critical to a safe outcome.
Additional information on loss of radio communications can be found in the US Aircraft Owners and Pilots Association (AOPA) Flight Training magazine, October 2005, Can you hear me now?
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
When the gear was selected down only the left main gear gave a down indication. The pilot carried out emergency extension procedures which resulted in a down indication for the right main gear. During the subsequent landing with the nose landing gear trailing, the lower fuselage and propellers were abraded.
Investigation disclosed that the hydraulic system had lost its oil overboard through the right engine hydraulic pump case drain. This occurred because the left engine driven hydraulic pump main shaft seals had been incorrectly assembled. The two seals are required to be placed back-to-back on the shaft, with one cup facing into the pump body and one facing away from the body. The seals had been placed with both cups facing away from the pump body.
This allowed the pump to force oil past the inner seal instead of the pressure acting to positively seat the seal onto the shaft. The pump was newly overhauled having been fitted to the engine on the day prior to the accident. It had completed one flight of 1.7 hours duration. Although the hydraulic reservoir contains an emergency oil supply, it is suspected that foaming of the contents due to pump cavitation precluded successful extension of all landing gears.
Significant factors
1. The seals on the main shaft of the right engine driven hydraulic pump were incorrectly installed.
2. The hydraulic oil was pumped overboard past the incorrectly installed seals.
3. The emergency oil supply was not able to successfully extend all three landing gears.
4. During the landing roll the nose landing gear collapsed.
The pilot conducted the flight to discover any remaining defects in the aircraft after it had been subject to a period of inactivity and repair. The pilot completed a full stop landing and planned to conduct some further recency circuit training before returning to Jandakot. The aircraft was subsequently landed with the landing gear retracted, after the pilot forgot to extend the gear.
VH-OXB departed Port Macquarie for Williamtown at 0922 hours and contacted Flight Service (FS) on Area frequency on climb to 8,000 ft.
VH-BIH departed Port Macquarie for Aero Pelican at 0923 hours and was climbing to 6,000 ft. The pilot initially reported on climb to 4,000 ft but this was later clarified.
Each aircraft was given traffic information on the other by FS.
As VH-OXB approached Taree the crew requested from FS an airways clearance to enter Williamtown controlled airspace (CTA) and were advised that they could expect a clearance at 4,000 ft. They consequently elected to descend outside controlled airspace (OCTA) to 4,000 ft and requested traffic information. The flight service officer (FSO) advised that there was no additional instrument flight rules (IFR) traffic.
As VH-OXB passed Taree the crew were instructed to contact Williamtown air traffic control (ATC) for an airways clearance, which they did. Williamtown ATC were unable to issue a clearance immediately due to traffic problems in CTA and instructed VH-OXB to remain OCTA to await clearance. The crew initiated a turn at the CTA boundary (10 NM south of Taree) and commenced a holding pattern that took the aircraft northbound towards Taree. No radio transmission was made to indicate this change of track.
During the northbound leg of the holding pattern, Williamtown ATC advised the crew of VH-OXB that a clearance could now be expected at 5,000 ft and the crew commenced climb to that altitude in preparation for the clearance. No radio transmission was made on Area frequency to indicate this change of level.
VH-BIH also requested an airways clearance from Williamtown ATC via Sydney FS and was also told to expect a clearance at 4,000 ft. The pilot then announced his descent to 4,000 ft and clarified his current 6,000 ft altitude with FS. The FSO advised the pilot that there was no IFR traffic, he believed that the traffic advice given earlier would still be considered current by the pilots of both VH-OXB and VH-BIH.
VH-BIH was now overhead Taree and changed frequency to contact Williamtown ATC and request his airways clearance. As he did so the pilot saw VH-OXB immediately ahead and at the same level. He took evasive action by increasing the rate of descent of his aircraft and passed underneath VH-OXB. VH-BIH was equipped with a single radio only and the pilot was unable to monitor the Williamtown ATC frequency prior to Taree.
The aircraft passed within approximately 100-150 ft.
Significant Factors
1. The Sydney FSO assumed that both pilots would consider that traffic information passed to them on departure Port Macquarie would remain current for the duration of their flight.
2. Williamtown ATC elected to use different altitudes in accordance with the original planned levels, rather than the actual levels at the time.
3. The pilot of VH-BIH had only one radio.
4. The crew of VH-OXB did not make an area frequency transmission advising either their change of track or change of altitude.
Safety Action
As a result of this investigation the RAAF initiated a variation in their instruction of traffic management techniques for controllers operating the Williamtown low level airspace.