On 22 June 2019, a Robinson Helicopter Company R22, registered VH-HHQ, departed Kutchera Station, Queensland to perform mustering operations. During mustering, as the pilot was manoeuvring the helicopter, the right tail rotor (or anti-torque) pedal cracked and became stuck. The pilot was unable to dislodge the pedal and prepared for an immediate landing in accordance with the stuck pedal procedure. Just prior to landing, the helicopter struck a tree and became uncontrollable. The aircraft impacted the ground and although the pilot was uninjured, the helicopter was substantially damaged.
What the ATSB found
Following examination of the helicopter by the maintenance organisation, a significant fracture was noted at a weld located on a right angle join between two sections of tube. The right pedal was removed from the helicopter and sent to the ATSB for further examination and testing. The ATSB found that the pedal had fractured as a result of a fatigue failure, which had initiated at the welded joint, and progressed until the remaining section of the tube could no longer sustain the in‑service loads. It was considered likely that a pre-existing crack had initiated at the highest stress part of the component, and had opened up following the load applied during the manoeuvre described by pilot, rendering the pedal unserviceable.
The tail rotor pedal had been recently inspected as part of routine maintenance and while it was considered likely that the developing crack was present, it was not detected at that inspection. However, it was considered that this was due to the inherent difficulties associated with inspections at the location of the cracking.
What has been done as a result
While not required as part of the routine inspections, the maintenance organisation has added the tail rotor pedals to the list of components that undergo magnetic particle inspection at each 2,200‑hour overall.
Safety message
The location of the fatigue crack in this accident highlighted the need to be vigilant when performing inspections in difficult or hard to reach places. In the case of the tail rotor pedal, the inspection was made difficult due to the location, and required a torch and mirror to inspect a matte black surface.
Additionally, the quick thinking actions of the pilot following the failure resulted in a good outcome, with no injuries reported.
The investigation
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 22 June 2019, the pilot of a Robinson Helicopter Company R22 helicopter, registered VH‑HHQ, departed Kutchera Station, Queensland to perform mustering operations. While mustering, the pilot applied a small amount of right tail rotor (or anti-torque) pedal[1] to manoeuvre the helicopter to turn back in the opposite direction. During this time, and as the pilot reported repositioning in the seat, the right pedal cracked, which caused it to bend forward and become stuck. The pilot grabbed the right pedal in an attempt to free it and allow the use of the left pedal, but was unable to do so. The pilot continued the flight to the nearest safe cleared area to land and commenced the jammed pedal procedure.[2]
When about 50 ft above ground level, as the pilot was preparing to perform a running landing,[3] it was reported that a gust of wind hit the helicopter from an angle, causing it to spin. The helicopter then hit a tree and then became uncontrollable before coming to rest on the ground. The pilot shutdown the helicopter and exited. There were no reported injuries, however, the helicopter was substantially damaged.
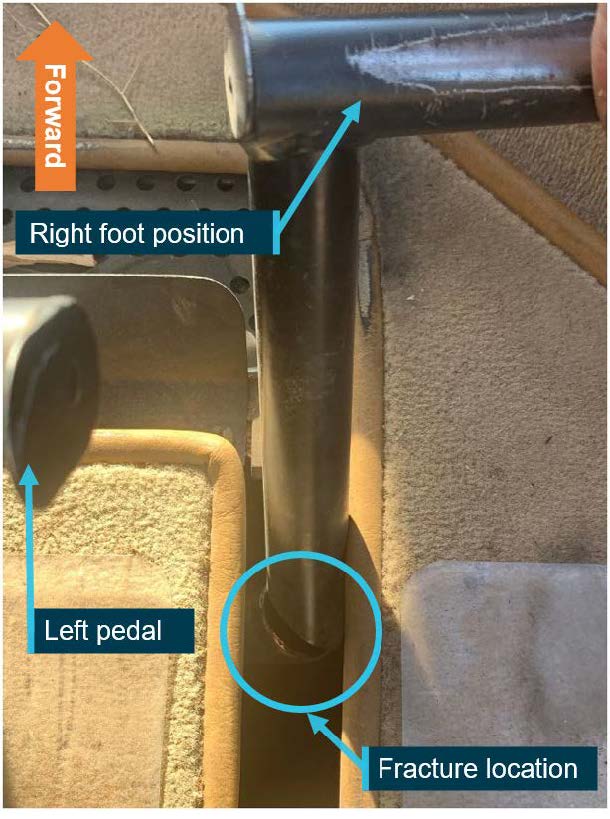
Following examination of the helicopter by the maintenance organisation, a significant fracture was noted on the right tail rotor pedal assembly at a weld located on a right angle join between two sections of thin walled tube (Figure 1). This join was between the vertical section of tube where the pilot places their foot, and the horizontal tube connecting to the tail rotor controls, and sits slightly below the cabin floor. The pedal was removed from the helicopter and sent to the ATSB’s technical facilities in Canberra for further examination and testing.
Figure 1: Fractured right tail rotor pedal as installed on VH-HHQ
Source: Operator, annotated by the ATSB
Context
Tail rotor pedal examination
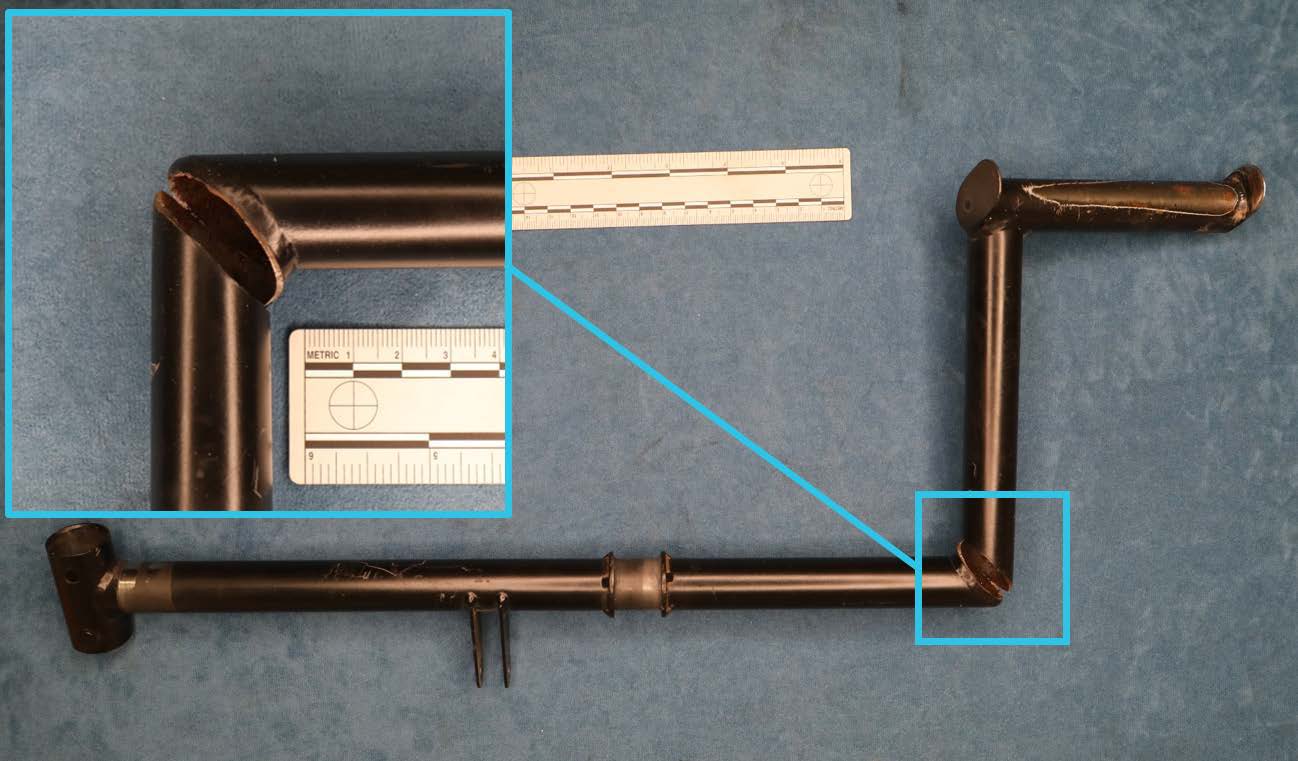
The ATSB’s initial examination of the right tail rotor pedal (part number A330-1), which had a matte black surface, found that:
The weld had fractured on the side of the pedal closest to the pilot seat (Figure 2).
While the fracture was not through the entire section of the tube, the pedal assembly was no longer capable of maintaining loads and transferring pilot inputs.
The pedal did not show any evidence of dints, scratches or other signs of mechanical damage.
Wear, in the form of missing paint and a shiny smooth surface, was observed on the pedal surface in contact with the pilot’s foot.
Some evidence of corrosion product was observed within the tubes. Robinson advised that this was the first known occurrence of internal corrosion. As part of the manufacturing process, to ensure the removal of any residual moisture, a small breather hole was left open, and the entire assembly heated to remove any internal moisture, before the breather hole was welded shut. Robinson also advised that the amount of corrosion observed appeared to be more than residual moisture from manufacture. They stated that, as the tubes were completely sealed, there was no inspection to detect internal corrosion.
Figure 2: Right tail rotor pedal as received by the ATSB, showing the location of the fracture
Source: ATSB
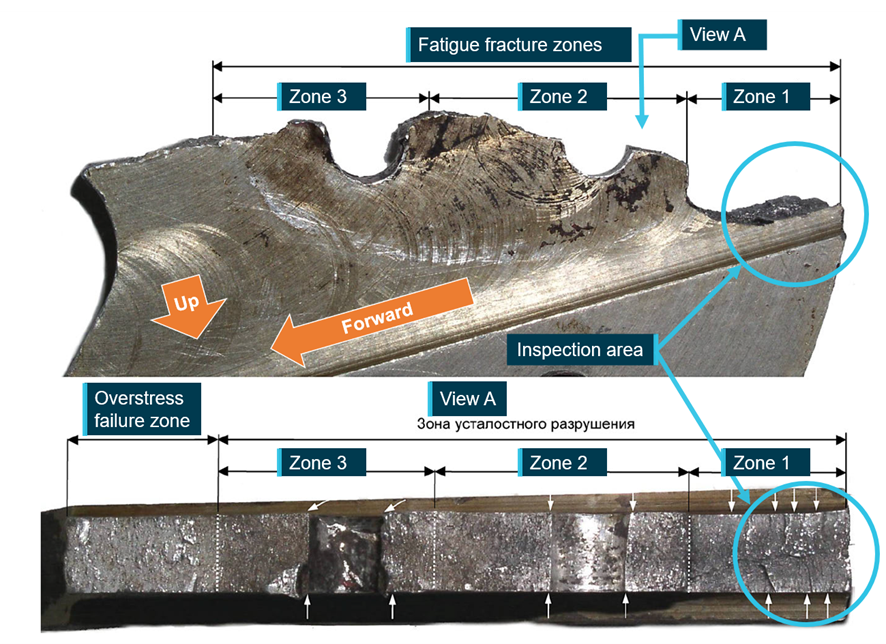
Following the initial examination, the pedal was fractured in the ATSB laboratory to separate and expose the two fracture surfaces. The majority of the fracture surface was discoloured and exhibited evidence of pre-existing cracking consistent with a fatigue failure (Figure 3). While the surface features were difficult to distinguish, the discolouration was indicative that the crack had been present for some period of time prior to the failure. While it appeared that the crack had initiated along the edge of the weld, no exact origin could be identified. However, the location of cracking was coincident with the location where the pilot input on the vertical tube was transferred to the horizontal tube, which is connected to the tail rotor push-pull tube assembly. As such, this area was subject to the largest torsional bending stress.
Figure 3: Right tail rotor pedal fracture surface following fracture by the ATSB
Source: ATSB
Following the examination of the fracture surface, it was then sectioned in the region adjacent to the likely origin for further inspection. The general fracture surface profile was consistent with a fatigue fracture. While the internal surface of the tube exhibited some evidence of pitting and general corrosion, there was no evidence that the crack initiated at one of these locations. Additionally, as the tubes were completely sealed, it was more likely that the corrosion product was the result of moisture ingress following the initiation of the fatigue crack.
The microstructure of the weld and tube was consistent with a low alloy steel in the heat-treated condition. A microhardness traverse test was conducted from the fracture surface through the weld heat affected zone into the parent metal and was consistent with the material type in the heat-treated condition. These observations complied with the information provided by the manufacturer.
Maintenance history
The helicopter (serial number 4071) had accumulated 5,828.4 hours total time-in-service at the time of the accident. Inspection of the tail rotor pedals was performed at both the 100-hourly inspection and 2,200-hour overhaul. The most recent 100-hourly inspection was performed 37.2 hours prior to the failure, while the 2,200-hour overhaul was completed in February 2017. At the 100-hourly inspection, the maintenance manual task for the pedals stated:
Inspect condition. Verify no cracks. Verify security and operating clearance.
There was no requirement to remove the bearing block cover plates, an access cover on the floor of the cabin, covering the horizontal portion of the rail rotor pedal. While the location of cracking in this occurrence was slightly under the cabin floor, Robinson advised that the affected weld would normally be visible using a torch and a mirror during the inspection. They also advised that the pedal needed to be moved forward and backward to see both sides. In addition to the 100-hourly inspections, at each 2,200-hour overhaul the pedals were removed for closer inspection.
The manufacturer further advised that, where maintenance was undertaken at a field service centre, as was the case for VH-HHQ, the pedals were subject to visual inspection only. However, if the overhaul was performed at the Robinson factory (not available in Australia), the pedals would be examined using a magnetic particle inspection (MPI).[4] This technique would be more likely to identify surface defects, as the paint would be removed prior to the testing, and the contrasting nature of the test medium would mean that cracks would be highly visible.
Similar failures
Robinson advised that they were aware of previous in-service fractures near the weld, however, the cause was either attributed to a modification to the assembly which involved some type of pedal extension (one case) or impact/mechanical damage. A search of the Civil Aviation Safety Authority’s defect report service and ATSB occurrence databases for the previous 10 years did not identify any other similar failures.
Safety analysis
While manoeuvring during mustering operations, the right tail rotor pedal failed and became stuck. The pilot elected to land immediately, but during this, the helicopter struck a tree. The helicopter became uncontrollable and impacted the ground, resulting in substantial damage.
The tail rotor pedal failed as a result of a fatigue failure at a right angle welded joint between two sections of thin walled tube. While the ATSB’s examination identified that the fatigue failure had initiated adjacent to the weld line, the exact origin could not be determined. This location of the cracking was also coincident with the point of maximum torsional bending stress in normal operation. The microstructure and hardness of the tube and weld were consistent with the requirements as specified by the manufacturer.
The pedal had undergone a visual examination at the most recent 100-hourly inspection. While it was likely the crack was present at this inspection, the nature and location of the crack would have made it inherently difficult to detect. The developing fatigue crack would have initially presented as a hairline feature, and it was located on a matte black surface, at a change in section slightly below the level of the cabin floor.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the tail rotor pedal failure and collision with terrain involving Robinson R22 helicopter, VH HHQ near Kutchera Station, Queensland, on 22 June 2019.
Contributing factors
While conducting mustering operations, the right tail rotor pedal failed due to fatigue cracking. During the subsequent emergency landing, the helicopter struck a tree and became uncontrollable, before coming to rest on the ground.
Due to undetermined reasons, a fatigue crack had initiated adjacent to a weld at a high stress location on the pedal. It was likely that the crack had been present at the most recent maintenance inspection, but the location of the weld may have made it difficult to detect in-situ.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Increased maintenance inspections
As a result of this accident, the maintenance provider has advised that, although not required by the maintenance manual, the tail rotor pedal assembly will now be included with other components that are sent for magnetic particle inspection at every 2,200-hourly overhaul.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
the pilot
Robinson Helicopter Company
the helicopter owner and maintainer.
References
United States Federal Aviation Administration (2019), Helicopter Flying Handbook, FAA-H-8083-21B.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the pilot
the helicopter owner
the helicopter maintainer
Robinson Helicopter Company
National Transportation Safety Board
Civil Aviation Safety Authority.
Any submissions from those parties were reviewed and, where considered appropriate, the text of the draft report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 5 June 2019, the pilot and passenger of a Yakovlev Aircraft Factories Yak-52 aircraft, registered VH-PAE, were conducting a private aerobatic flight from Southport Airport, Queensland. During the flight, while near South Stradbroke Island, the aircraft collided with water. The occupants were fatally injured and the aircraft was destroyed.
What the ATSB found
The ATSB found that, during the flight, a number of aerobatic manoeuvres were conducted below 500 ft above ground level. However, in the absence of recorded data or witnesses to the collision with water, it could not be determined with certainty that the pilot was conducting an aerobatic manoeuvre immediately prior to the impact, but it was considered a possibility. Despite this, for reasons undetermined, the aircraft collided with water at high speed.
It was also established that, during the accident flight and previous flights, the pilot conducted low‑level aerobatics without completing the required training or having the appropriate endorsement. This would have potentially limited the pilot’s appreciation of the risks associated with low-level aerobatics.
Some of the pilot’s low-level aerobatic flights had been witnessed by people with aviation experience and knowledge. While the pilot did receive some warnings about this, there were other opportunities and means for people to formally communicate and escalate their concerns that were not used.
Although not contributory to the accident, a pre-existing fatigue crack was found in the elevator bellcrank, which had the potential to fail in-flight, leading to a loss of control. In addition, the manufacturer could provide airworthiness information upon request for Yak-52 aircraft in Russia and overseas as long as they had not exceeded their prescribed airframe life. However, aircraft such as VH-PAE had exceeded their airframe life and therefore were no longer able to be supported. As a result, significant changes to the scheduled maintenance program relating to the elevator bellcrank were not known or included in local maintenance schedules.
Further, the ATSB established that VH-PAE, along with other Yak-52 aircraft, had exceeded their prescribed airframe life limit. Until 2007, permit index assessments were conducted by the Civil Aviation Safety Authority and included aircraft that had exceeded their life limits. While not related to the accident, when the Australian Warbirds Association Limited conducted the assessments, they did not consider Yak‑52 aircraft to have an airframe life. Subsequently, these aircraft were assigned a permit index that allowed flight over populous areas without consideration of the risk to the aircraft occupants and general public.
What’s been done as a result
In November 2020, the ATSB issued a safety advisory notice to Yak-52 maintainers and owners emphasising the importance of dye penetrant inspections to remove defective elevator bellcranks from service. The notice also noted that Russia, as the aircraft’s state of design, increased the frequency for inspections of the bellcranks to 25 ± 5 flying hours. Further, aluminium alloy bellcranks were no longer approved for use on Yak-52s operating in Russia.
Safety message
This accident highlights the inherent risks associated with performing low-level aerobatics and the reduced safety margins when recovering from manoeuvres. Even more so, it demonstrates the importance of being suitably trained and qualified to conduct these operations. It also provides an opportunity to encourage witnesses, particularly those within the aviation industry, to report any concerns regarding unsafe behaviours through mechanisms such as confidential reporting systems.
Further, as the Yak-52 aluminium elevator bellcranks have a propensity to crack, it emphasises the need to conduct more frequent dye penetrant inspections to identify and remove defective bellcranks from service, and to consider replacing them with steel bellcranks.
The occurrence
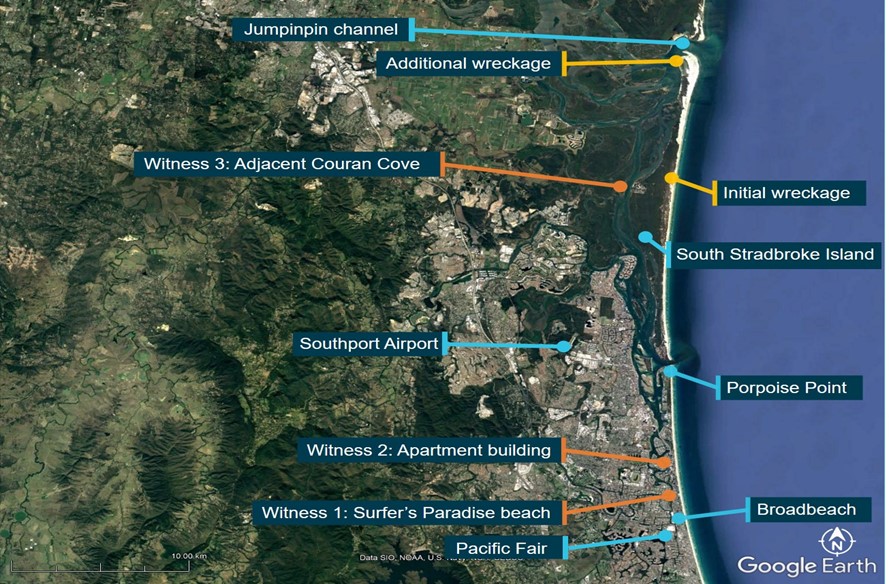
On 5 June 2019, at about 0945 Eastern Standard Time,[1] the pilot and passenger of a Yakovlev Aircraft Factories Yak-52 aircraft, registered VH-PAE, were conducting a private flight from Southport Airport, Queensland. The flight was intended to take about 30 minutes and included a scenic flight north along the coast from Broadbeach to the Jumpinpin channel, and then seawards off Jumpinpin to conduct aerobatic manoeuvres over water, before returning to Southport (Figure 2). A second passenger was waiting at the airport to complete a similar flight once the aircraft had returned.
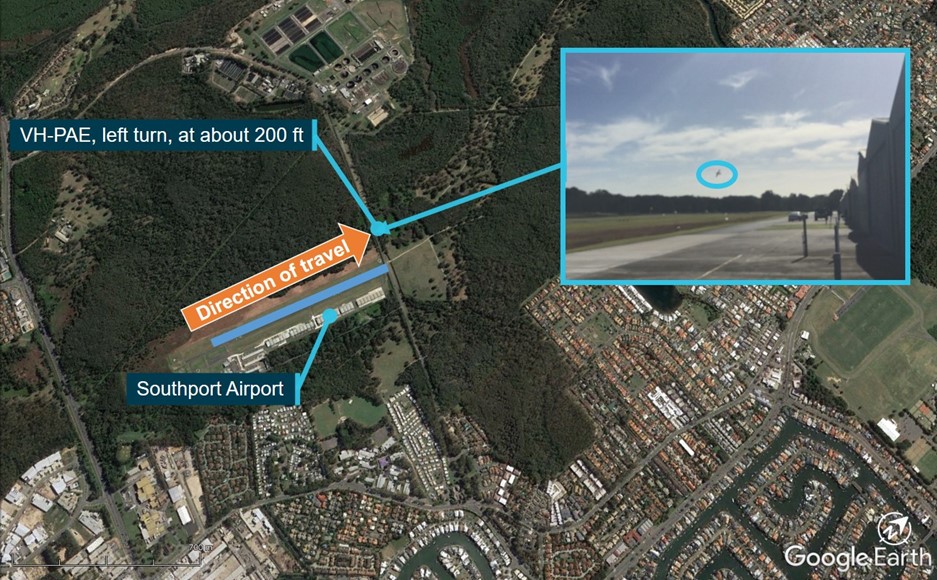
Prior to take-off, the pilot told a witness that a low-level turn over the trees would be more exciting for the passenger. The pilot also discussed taking off downwind on runway 01 and that the aircraft could accept the tailwind component. The second passenger provided video footage showing the aircraft departing Southport from runway 01 and conducting a left turn shortly after take-off. The ATSB’s analysis of that video estimated the turn was conducted at about 200 ft above ground level (AGL) (Figure 1). This departure was described by a witness at Southport as being ‘normal’ for the pilot. The aircraft was held close to the ground after take-off to build up airspeed, which allowed a left turn to be performed just past the runway boundary.
Figure 1: Take-off from Southport Airport and left turn (inset)
Source: Google Earth and witness, annotated by the ATSB
At 0950, Airservices Australia surveillance data identified a radar return for an aircraft tracking in a southerly direction from the airport. On reaching Broadbeach, the aircraft then turned left to commence tracking to the north along the coast. This was consistent with the timing of departure and proposed flight plan for VH-PAE.
Shortly after, the pilot was heard broadcasting on the common traffic advisory frequency by another pilot who departed Southport Airport at around the same time indicating they were overhead Pacific Fair (a shopping centre located at Broadbeach) at an altitude of 500 ft, northbound.
Two witnesses reported observing the aircraft tracking on the planned scenic route. The first witness was at Surfers Paradise beach (Figure 2) and observed the aircraft flying from west to east, then northbound along the coast (refer to section titled Witness observations). The second witness was near South Stradbroke Island on the 12th floor of an apartment building. That witness saw the track north along the beach towards South Stradbroke Island with two people on board.
Another pilot who recently departed Southport Airport, heard the pilot of VH-PAE broadcast on the common traffic advisory frequency that they were at Porpoise Point and heading seaward for aerobatics at 3,500 ft.
At about 0958, Department of Defence surveillance data recorded an aircraft over South Stradbroke Island, conducting operations with significant track and speed fluctuations, consistent with aerobatic manoeuvres. Altitude data was not available (refer to section titled Recorded information). About 7 minutes later, no further radar returns were recorded. Witnesses on the western side of South Stradbroke Island adjacent to Couran Cove, reported that they observed an aircraft consistent with VH-PAE conduct a 'loop, cut right, and dive below the tree line’, but did not recall anything else unusual about the aircraft.
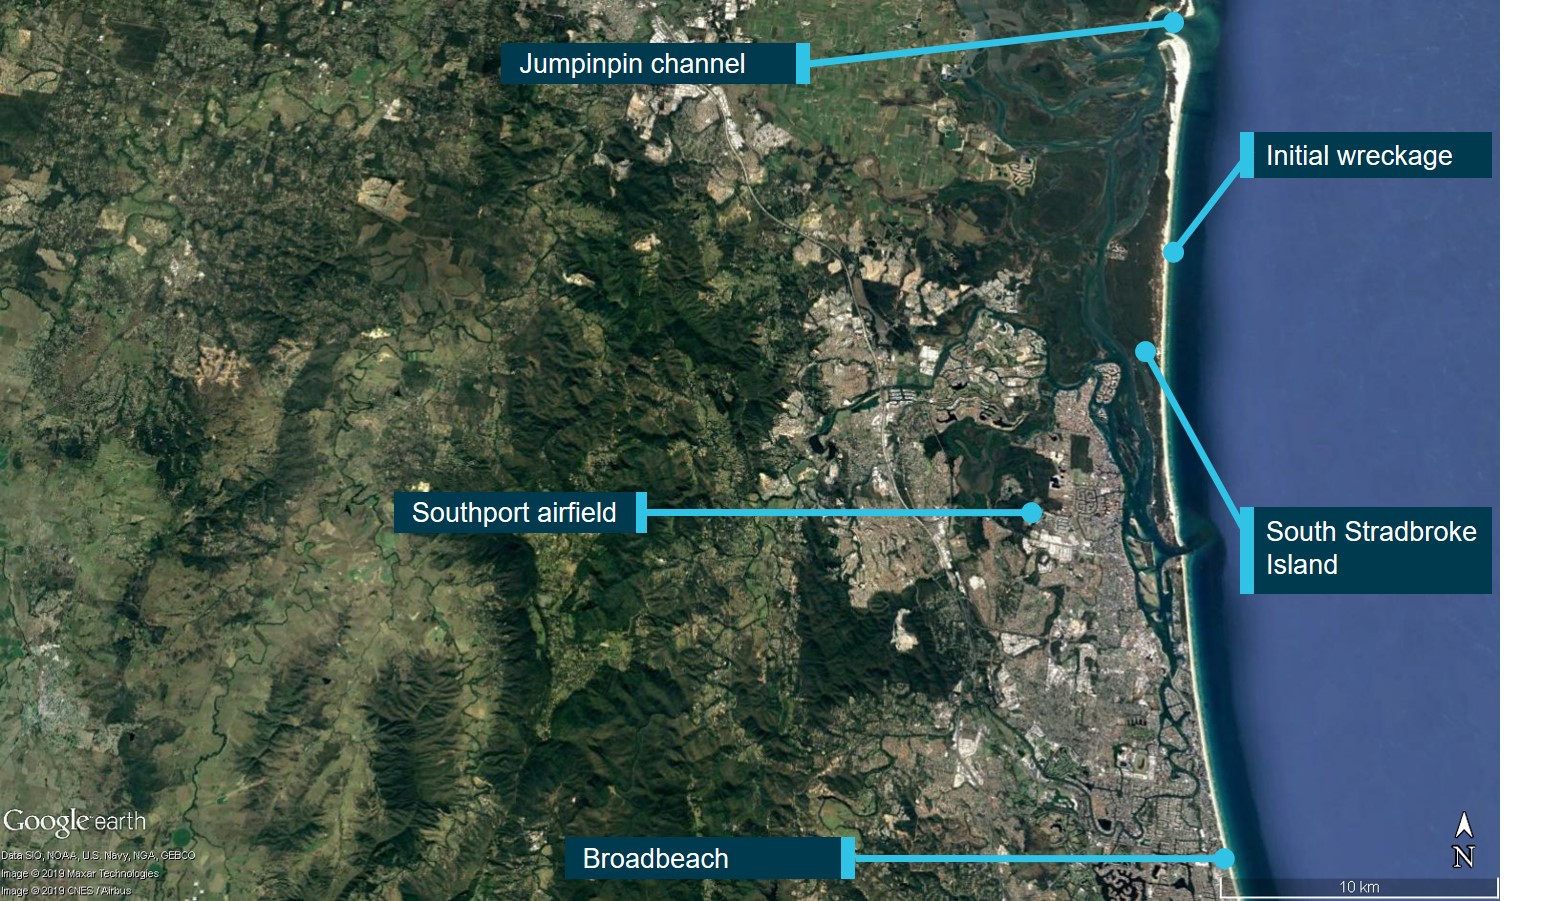
When the aircraft had not returned to Southport after an hour, the second passenger became concerned and asked members of the Southport Flying Club if they had heard anything. At about 1310, a representative from the club contacted Airservices Australia about the overdue aircraft and at 1400, the Australian Maritime Safety Authority’s Joint Rescue Coordination Centre initiated search and rescue operations. At about 1630, part of the propeller (initial wreckage) was located on the eastern side of South Stradbroke Island (Figure 2). In the following days, the pilot and passenger, who sustained fatal injuries were recovered, along with additional wreckage.
Figure 2: Location of areas of interest for the flight (blue), witness locations (orange), and aircraft wreckage locations (yellow)
The pilot held a current Private Pilot Licence (Aeroplane) initially issued under Civil Aviation Regulations 5[2] in 4 July 2014 and transferred to the Part 61 licencing system on 23 May 2016. The pilot’s general aviation logbook showed a total flying experience of 412.4 hours to the last recorded flight on 31 May 2019, of which 39.4 hours were in VH-PAE.
The pilot had last completed a single‑engine aeroplane flight review on 17 January 2019, which included an aerobatic flight activity endorsement. This qualified the pilot to conduct spins and aerobatics at no less than 3,000 ft AGL. After obtaining this endorsement, the flying instructor discussed the requirements for obtaining a low-level aerobatic endorsement (below 3,000 ft) with the pilot. However, the pilot did not obtain this endorsement nor hold an operational rating for low‑level flying.
The Civil Aviation Safety Authority’s (CASA) Part 61 Manual of Standards outlined that, aerobatic flight activity endorsements require pilots to operate no lower than the minimum authorised height of 3,000 ft AGL. Once proficient, and then checked for competency to the requirements of the standards, there is a progressive reduction in the minimum authorised height to 1,500 ft AGL, 1,000 ft AGL, 500 ft AGL, and then unlimited.[3] This process requires pilots to demonstrate competence at, or above each level before attempting the next level.
The pilot also held a Recreational Aviation Australia (RAAus) pilot certificate, issued in February 1999, and had accumulated a total of 413.3 hours up to 29 May 2015 with this certificate. There was no logbook for the pilot’s RAAus flying available and no further update of flying hours was noted on the RAAus pilot licence file after this date.
Medical and pathological information
The pilot held a Class 2 Aviation Medical Certificate, valid until 1 May 2021, and was required to have vision correction available for reading while exercising the privileges of the licence. A review of the pilot’s aviation medical records found there was no information that indicated a medical event may have contributed to the accident.
The nature of the pilot’s and passenger’s injuries limited the information that could be obtained from a post-mortem examination. Due to the disruption to the aircraft, the accident was not considered survivable.
Pilot’s flying history
An acquaintance described the pilot as initially ‘being disciplined’, but this had slipped as the pilot became more familiar with the accident aircraft and began ‘pushing limits too fast and too soon’. Another acquaintance mentioned having concerns about the height the pilot flew aerobatics and attempted to communicate these concerns. There were also a number of occasions in the years prior to the accident where the pilot was observed performing low-level flying and aerobatic manoeuvres without holding the required qualifications:
In October 2013, the pilot received a written warning from RAAus about performing aerobatics in an RAAus registered aircraft, which was not permitted.
In November 2018, the pilot was observed to conduct low-level aerobatic manoeuvres in the accident aircraft at about 500 ft over a residential area near Southport Airport, which was counter to the ‘flying neighbourly'[4]policy. As a result, the pilot was issued with a verbal warning by the Southport Flying Club and advised that a repeat incident would result in a revoked membership from the club.
A friend of the pilot went for a flight in late April 2019. The friend reported flying low-level as they were at the same height as the buildings along the beach and conducting aerobatic manoeuvres. An analysis of the passenger’s video footage showed that the aerobatics were conducted below 1,000 ft and that elements of the flight were conducted as low as 260 ft based on the buildings in the area. The friend recalled that the pilot had commented about knowing how to safely do a barrel roll[5] while flying low-level. The pilot had also mentioned not being approved to conduct this manoeuvre at a low height and that if too much height was lost, it would be ‘impossible’ to recover.
About a week prior to the accident, the pilot was observed to enter the circuit at Boonah airfield inverted, estimated to be at about 1,300 ft by a witness.
Three days prior to the accident, another passenger who flew with the pilot reported the flight was lower than the height of the buildings on the Gold Coast. Images provided showed the flight was conducted below the height of numerous well-known buildings at that location, which was below 500 ft.
A review of the ATSB and CASA databases found no safety reports relating to the pilot. In addition, aside from the verbal warning, the Southport Flying Club had not received any other safety reports regarding the pilot’s flying.
Aircraft information
General
The Yakovlev Aircraft Factories Yak-52 is an all-metal, two-seat, low-wing aircraft, powered by an air-cooled M-14P radial engine driving a two-bladed, variable-pitch wooden propeller. The aircraft was manufactured with front and rear flight controls. The primary flight controls are located in the front cockpit and the secondary flight controls in the rear cockpit. About 1,800 Yak-52 aircraft were produced between 1977 and 1998, which was designed as a military trainer. In 2020, there were 51 Yak-52s registered in Australia.
The accident aircraft was manufactured in 1982 by Aerostar in Bacău, Romania. In 2002, the aircraft reached the end of its airframe life and was disposed of.[6] In about 2004, the aircraft was disassembled in Russia and imported to Australia. The aircraft was first registered with the Civil Aviation Safety Authority on 5 April 2017, and was registered to the pilot on 5 July 2018. The last periodic and associated inspections were carried out on 31 October 2018. The most recent entry on the maintenance release was 5 days prior to the accident (on 31 May 2019) and showed that the aircraft had accumulated 1,164.2 hours total time‑in‑service.
A review of the weight and balance found that the aircraft was within centre of gravity limits at the time of take-off. Further, the aircraft was not fitted with a transponder, nor was it required to be.
Airworthiness
The majority of ex-military (commonly referred to as warbirds) or replica aircraft in Australia were not designed and manufactured to any known civil aviation standard. These aircraft have been allowed to operate in Australia under a special certificate of airworthiness in the limited category.[7] The special certificate of airworthiness, issued for VH-PAE on 19 September 2017, indicated the aircraft was to be operated in day visual flight rules[8] conditions.
As an ex-military aircraft, under Civil Aviation Safety Regulation 1998 (CASR) Part 132 it was required to be administered by the Australian Warbirds Association Limited (AWAL). AWAL is a self-administering recreational aviation administering organisation operating under CASR Part 132. Part of their role was to provide oversight of this sector of warbird, ex-military and replica aircraft. As such, aircraft operated under CASR Part 132 must conform to the requirements of the AWAL exposition and self-administration manual. All persons who fly an AWAL administered aircraft are to be members of AWAL.
The AWAL contacted the ATSB shortly after the accident and stated that the aircraft was purchased in about May 2018 and that the aircraft’s annual renewal with AWAL subsequently expired. Sometime later, the aircraft was observed to be operating and after attempts to contact the new owner, this was reported to CASA. The aircraft’s annual AWAL renewal was subsequently paid and the new owner became a member of AWAL, in order to operate the aircraft.
There were different design and manufacturing standards of warbird aircraft in Australia. The aircraft was maintained in accordance with AWAL’s maintenance schedule, which included the applicable airworthiness directives. In addition, the AWAL maintenance schedule included structural integrity inspection requirements, carried out every 3 years. This specified that engine mount and landing gear welds be inspected by using a 10 times magnifying glass or with dye penetrant. Other listed inspection requirements were to be carried out to a depth that the maintenance organisation performing the work deemed necessary.
Airframe life and permit index
Airframe life limits for Yak-52s as defined by the Yakovlev Design Bureau were conditional on the aircraft being maintained in accordance with Yakovlev’s scheduled maintenance program. The airframe life for Yak-52s of the same specification as VH-PAE, was 1,000 flight hours or 5,000 landings in 20 years. In 2005, the Russian Central Aerohydrodynamic Institute (ЦАГИ) established an extension to the Yak-52 airframe life to 2,000 flight hours or 10,000 landings in 30 years. To support this extension, Yakovlev issued amendment 2 of the scheduled maintenance program for the Yak-52 on 9 September 2009 and the extension was conditional on the aircraft continuing to be maintained in accordance with the revised schedule. As VH-PAE and other imported Yak-52s stopped being maintained in accordance with any of the Yakovlev schedules when they were disposed of, the life extension did not apply.
Warbird aircraft in Australia, as part of their introduction to service, underwent a permit index (PI) assessment. CASA advisory circular Limited category aircraft - permit index (AC 21-25) outlined that this was a risk assessment procedure to:
…ensure that the risk is confined to the occupants of the aircraft, while protecting the general public from risk of harm or property damage.
PI assessments were initially carried out by CASA, who performed about two-thirds of these prior to their administration being transferred to AWAL in May 2007. At the time of its registration in Australia, VH-PAE was 15 years over its 20-year airframe life. A review of the other Yak-52s in Australia found that 40 per cent were over their airframe life limit at the time of registration. At the time of publication, and with the exception of some aircraft that have been modified to a tail-wheel configuration, the remaining Yak-52s registered in Australia had exceeded their airframe life.
PI numbers are issued to individual aircraft ranging from ‘0’ with no airport or populous area[9] restrictions (other than the normal airspace and air traffic control requirements), to ‘3’ where operations over populous areas were prohibited.
The assessment procedure takes into account a range of risk categories including fatigue history, repairs and modifications, installed equipment (i.e. ejection seats or external fuel), engine type, fuel capacity, stall speed, etc. The assessment adds or subtracts points against risk category elements. The total score determines the PI number. The risk category for fatigue history had the following elements:
history not known – deduct 130 points
airframe life exceeded – deduct 130 points
not applicable or airframe life within limits – no addition or subtraction of points.
Deducting 130 points, such as if the aircraft had an expired airframe life, would result in a PI assessment that would prevent operations of aircraft over populous areas.
The AWAL exposition and self-administration manual included a procedure for issuing a certificate stating an airframe life different to the aircraft’s currently approved airframe life.[10] It required the aircraft owner or registered operator to apply with the following information:
- the name of the applicant or registered operator - the make, model and registration of the aircraft - the approved airframe (fatigue) life of the aircraft - the expired fatigue life of the aircraft - how the fatigue has been measured - the operational history of the aircraft - the maintenance history of the aircraft - the proposed future use of the aircraft - whether it is proposed to use the aircraft for adventure flights - if a detailed inspection has been made of the aircraft structure, the reports of that inspection.
An assessment of the application by an AWAL approved person considered the following:
- the existing approved airframe life and the factors and assumptions on which it is based - the intended future operations of the aircraft - the operational and airworthiness history of the aircraft - the service history of: - other aircraft of the same type and model; and - other aircraft and structures of similar design - maintenance program findings - an assessment of the structure of the aircraft.
The AWAL approved person could issue a certificate stating a new approved airframe life if they were satisfied it would maintain an acceptable level of safety of flight.
In carrying out the PI assessment for VH-PAE, the risk category for fatigue history was recorded against the risk element ‘not applicable or airframe life within limits’, and included in the comment ‘No, fatigue life’. VH-PAE was assigned a PI of ‘0’ in 2017, and there was no record of a certificate stating an airframe life different to the existing approved airframe life being issued.
AWAL advised the ATSB that they did not regard the Yak-52 as having an airframe life as they had not been presented with documentation suitable to AWAL to define it, and from their experience they did not consider it to be an issue. AWAL further advised that, for this reason, a certificate to extend the airframe life of VH-PAE was not required, and that the PIs for other Yak‑52s were assessed as ‘0’.
In 1998, the United Kingdom (UK) Civil Aviation Authority (CAA) issued Mandatory Permit Directive[11] (MPD) 1998-017 to detail airframe life limitations and the overhaul life of the Yak-52 in the UK. It stated that:
Correspondence with the Design Authority, Yakovlev Design Bureau, has confirmed that there is an initial airframe life limit, which varies with the Series of the aeroplane.
The initial airframe life limit can be extended by the implementation of an approved maintenance and inspection programme.
The MPD defined the airframe life for Yak-52s as 1,000–1,500 flight hours or 5,000–7,000 landings in 15–20 years, depending on the modification status of the aircraft. AWAL advised they did not regard MPD 1998-017 as suitable data to define Yak-52 airframe life limits as they were not required to comply with data published by foreign authorities.
Fuel
The aircraft operated on aviation gasoline (AvGas) 100LL (91/96 octane) and had the capacity to carry 120 L in two 60 L wing tanks, with about 12 L being unusable. Southport Airport fuel records indicated that the pilot uplifted 75.22 L of AvGas prior to departure. A test of the fuel bowser found no issues with the fuel quality.
Meteorological information
Bureau of Meteorology
The nearest Bureau of Meteorology automatic weather station was located at the Gold Coast Seaway, about 12 km south from the last witness observation. At 1000 on the day of the accident, the station recorded the wind at 11 kt from a southerly direction and a temperature of 19.5°C.
Witness observations
Witnesses located near Couran Cove on South Stradbroke Island, at time of sighting the aircraft, described the conditions as ‘good’ visibility, with no cloud. There were light winds at the time, but wind gusts increased over the day.
Recorded information
Surveillance data was obtained from Airservices Australia (Mount Hargrave radar) and the Department of Defence (Mount Hargrave, Somerville and Amberley radars). As the aircraft was not fitted with a transponder, only primary radar returns[12] were available. The coverage will detect aircraft at, or above heights depending on the aircraft’s proximity to radar coverage and terrain shielding. Due to the limitations of primary radar and terrain shielding, there were gaps in the radar recording. An analysis of this data showed:
the aircraft was detected at 0946:43 departing Southport Airport and heading in a southerly direction
between 0952:13 and 0953:56, the aircraft was tracking in an easterly direction towards the coast
at 0955:27, the aircraft was tracking in a northerly direction towards South Stradbroke Island
until 0958:30, the aircraft had a relatively constant speed of around 120 kt, consistent with straight-and-level flight in a northerly direction along the beach
after 0958:30, the aircraft’s speed varied between 70 kt and 160 kt
between 1003:44 and 1004:30, the aircraft’s speed further reduced from 130 kt to 72 kt, and it was at or above 1,200 ft overhead South Stradbroke Island
the last detections between 1005:36 and 1005:48 were ‘tightly grouped’ indicating the aircraft was either at very low speeds or in a steep dive; the speed was below 60 kt, which could be attributed to the aircraft being in a vertical manoeuvre.
Department of Defence analysis of the aircraft’s recorded speed and heading variations indicated the manoeuvring was consistent with the conduct of aerobatics.
Witness observations
Several witnesses who observed the aircraft on the accident flight were interviewed by the ATSB. A summary of their recollections is provided below.
Surfers Paradise beach
At around 1000, a witness located at Surfers Paradise beach observed the aircraft turn and track along the beach in a northerly direction, conducting a manoeuvre consistent with a ‘split S’[13] turn. While tracking along the beach, the pilot then conducted another manoeuvre likened to an aileron roll.[14]
From the witness’ location, it appeared the aircraft was flying below the height of the buildings and was lower than other aircraft they had observed flying along the beach. Based on this, and a comparison of another aircraft present at the time of interview, VH-PAE was estimated to be flying between 200-300 ft.
The witness also recalled that the aircraft’s speed and engine sound was constant and there did not appear to be anything unusual. Further, the weather was described as ‘fine’, with a southerly wind.
Apartment building near South Stradbroke Island
Between 1000-1100, a witness on the 12th floor balcony of their apartment saw the aircraft tracking in a northerly direction along the coast, flying straight-and-level. The aircraft was at the same height as their floor, at an estimated 100-200 ft, which was lower than aircraft usually flying in that area and direction.
Couran Cove
Around 1100,[15] witnesses were on their houseboat on the western side of South Stradbroke Island near Couran Cove, about 5 km south of the Jumpinpin channel. On the south-east side of the island, they observed an aircraft consistent with the accident aircraft conduct a ‘loop’, ‘roll’, then ‘cut’ right, and then dived behind the tree line. The aircraft did not appear to lose height after conducting the loop. The witnesses did not recall any unusual engine noises, nor did they see or hear anything that suggested the aircraft had collided with water.
Wreckage and impact information
Search area and recovered wreckage
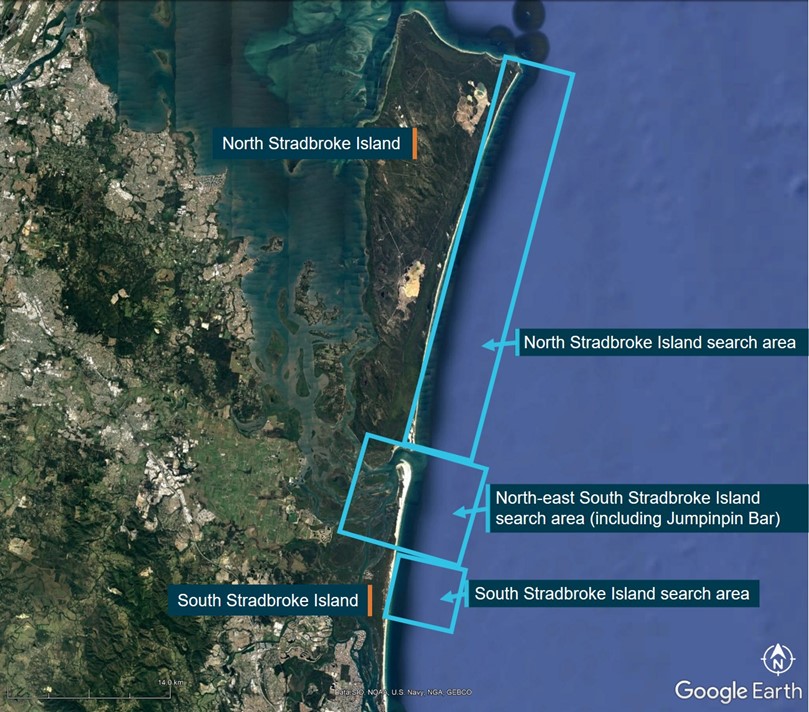
The Australian Maritime Safety Authority and Gold Coast Water Police initiated a search for the aircraft and occupants. The search zones were around North Stradbroke Island and to the north‑east coastline of South Stradbroke Island, including the Jumpinpin channel (Figure 3). The search was interrupted for several days due to poor weather conditions. When the search resumed, it focussed on the South Stradbroke Island area, where most of the recovered wreckage was found.
Figure 3: Search area
Source: Google Earth and Queensland Police Service, modified by the ATSB
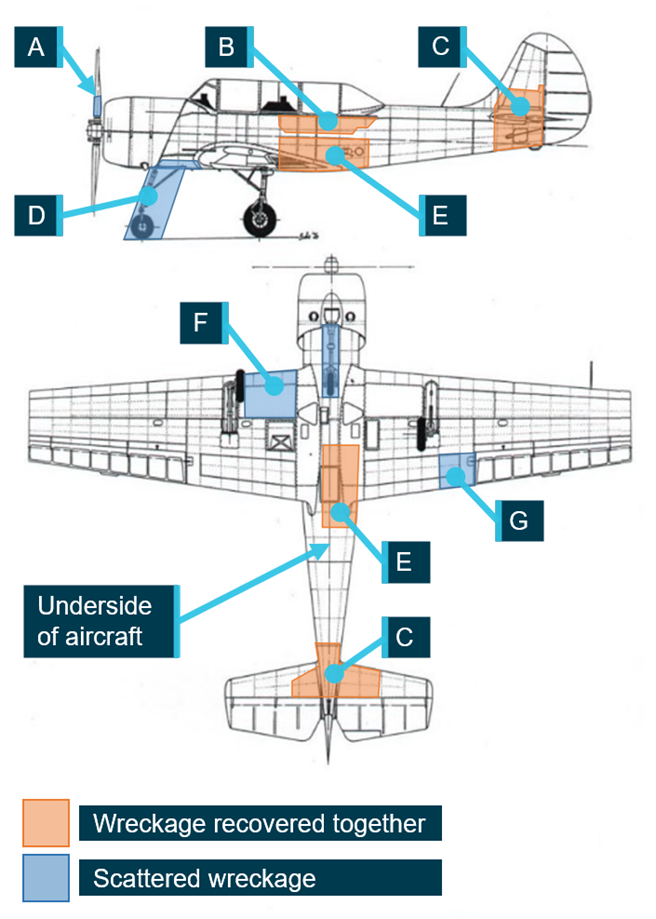
The recovered wreckage, depicted in Figure 4, included:
a number of wooden propeller blade fragments (A)
the fuselage skin and structure from the left side of the rear cockpit (B)
the tail section consisting of the rear fuselage and the inboard sections of the horizontal and vertical stabilisers (the tail section was found attached to the rear cockpit by the flight control cables) (C)
the nose landing gear, its associated components and mounting structure (this structure formed the floor of the front cockpit and included the front cockpit rudder pedals) (D)
a number of components from the front and rear cockpits, with the rear cockpit in place but significantly disrupted (E)
a section of the right wing inboard leading edge (F)
a section of the left-wing trailing edge adjacent to the aileron (G).
In addition, a seat cushion base and back, and the pneumatic system main and emergency storage tanks were also recovered.
Figure 4: Shaded areas showing the wreckage recovered from VH-PAE
The recovered wreckage was transported to secure facilities at the Gold Coast Water Police station for examination by the ATSB. That examination identified that the left-wing rear mount was present with a section of the wing structure.[16] The failure of the wing structure was likely to have been due to overstress and the failure surfaces had been eroded during their time in the ocean prior to recovery.
The left-wing trailing edge included the hinge point for the left aileron and the hinge bracket from the left aileron. The cut-out for the left flap was present along with a section of the wing upper surface skin. The inboard section of the upper surface was torn in an irregular fashion. The outboard section of the upper surface was torn along a rivet line.
The right-wing skin had been torn away from the spar. There was significant disruption to the leading edge. The right-wing fuel tank had been ejected from this section. Remnants of its mounting frames and straps were present. The impact damage to the aircraft meant it was not possible to determine the quantity or quality of the fuel on board prior to the accident. The majority of the lower surface of the recovered wreckage was the right-wing fuel tank access panel. This panel showed evidence of surface hydraulicing,[17] likely resulting from the impact with the water.
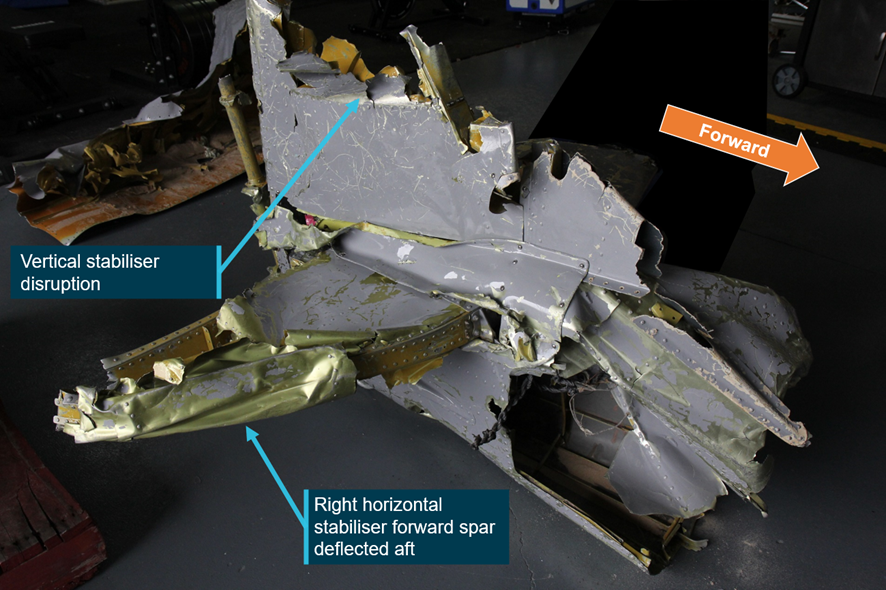
Examination of the tail section of the aircraft found the right horizontal stabiliser was extensively damaged with its forward and rear spars bent rearwards and stabiliser skin torn away from the structure (Figure 5). The centre hinge for the elevator was bent inboard. The left horizontal stabiliser had tearing mid-span, but otherwise it retained its original form. The vertical stabiliser was extensively damaged with most of its upper section missing. Further, the wreckage examination identified two small cracks on either side of the elevator bellcrank at a change in section (refer to section titled Bellcrank examination).
Figure 5: Tail section damage
Source: ATSB
A significant amount of the aircraft structure and systems were not recovered. However, from the wreckage available for examination, there was no evidence of any pre-impact failures. The significant disruption to the aircraft was indicative of a high-speed impact with significant impact forces, which were not considered survivable.
Elevator bellcrank assembly
Bellcrank examination
The elevator bellcrank is primarily loaded in the vertical plane and transmits the forward and rearward pilot inputs on the control column through the cables to control elevator movement. The ATSB’s initial examination of the elevator bellcrank identified two small cracks on either side at the location identified in previously published airworthiness directives (refer to section titled Airworthiness requirements) (Figure 6). The larger crack on the right side (aft looking forward) was relatively straight and extended about 3 mm across the rear face of the bellcrank and 10 mm along the side. A number of small indents were observed in the region of the crack. Closer examination of the crack on the left side revealed that it was two smaller cracks. One crack was located on the rear face corner, extending about 1 mm each direction, and the other followed the machined radius and extended for about 7.5 mm.
In order to perform further analysis on the cracking, the bellcrank was fractured to examine and categorise the cracks. This examination identified that the smaller cracks on the left (aft looking forward) showed features consistent with fatigue and were likely present prior to the accident. The larger crack’s features were predominantly consistent with overstress as a result of the accident.
A chemical analysis of the bellcrank found it had been manufactured from AK-4 aluminium alloy, which may have been an earlier specification due to the age of the aircraft. The most recent design specification was for the bellcranks to be manufactured from AK-6 aluminium alloy. The radius at the change in thickness from the inner to the outer section of the bellcrank was relatively consistent with that specified on the supplied engineering drawings from the manufacturer.
Figure 6: Elevator bellcrank cracks observed on VH-PAE
Source: ATSB
Previous Yak-52 elevator bellcrank failure
On 19 September 2010, in Yekaterinburg, Russia, a Yak-52 conducting aerobatics was observed by witnesses to enter a steep descent. The pilot reported a broken cable within the aircraft. The pilot was unable to regain control and the aircraft collided with terrain. The pilot was fatally injured and the aircraft was destroyed in a post-impact fire. The investigation outcomes were detailed in a paper published by the Russian Association of Independent Aviation Accident Investigators.
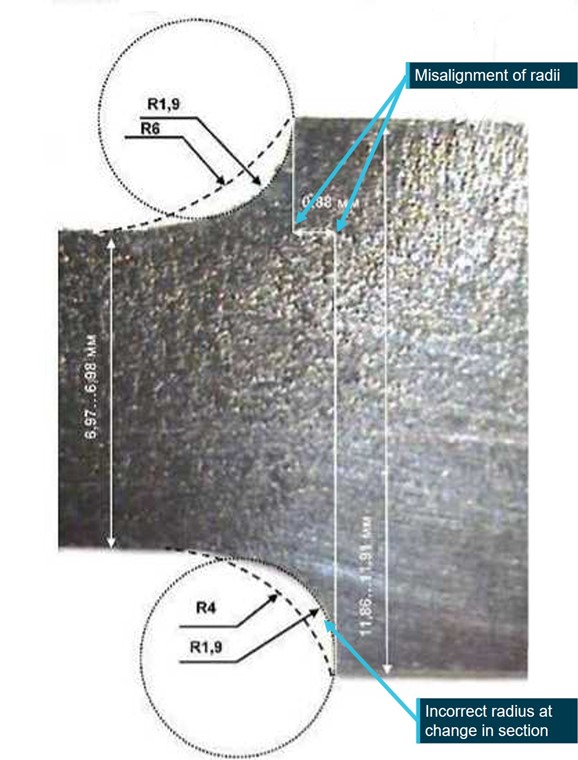
An examination of the wreckage found that the elevator bellcrank had fractured through the inner section, adjacent to the change in section from the inner to the outer section (see Appendix - Photographs of the elevator bellcrank from the 2010 accident). Examination of the fracture surface showed it was consistent with a fatigue failure. The bellcrank was found to have been correctly manufactured from AK-6 aluminium alloy according to the design specification for this aircraft having been manufactured in 1990. The paper concluded that high operational cyclic stresses had influenced the development of the fatigue crack, along with multiple aspects relating to the manufacture of the elevator bellcrank including:
a radius at the change in section (thickness) on the bellcrank was smaller than that specified in the engineering drawings
when manufactured, the radii on either side of the bellcrank were incorrectly aligned (Figure 7)
an unfavourable (lateral) microstructure orientation[18]
rough machining surface at the crack origin.
Figure 7: The bellcrank from the Yak-52 involved in the 2010 Yekaterinburg accident showing misalignment of the radii and incorrect radius at the change in section
Source: Society of Independent Air Accident Investigations, modified by the ATSB
The Russian investigation examined an elevator bellcrank from an exemplar aircraft that was manufactured around 1985. This bellcrank was cracked in the same area, had manufacturing defects, and was manufactured from AK-4 specification aluminium alloy. It was noted this may have been an earlier specification due to the age of the aircraft.
Airworthiness requirements
While the presence of the pre-existing cracks did not contribute to the accident involving VH-PAE, they were coincident with the location identified in the airworthiness directives and a service bulletin issued by Lithuania and the UK. Mandatory Permit Directive MPD 2000-004 was issued by the UK Civil Aviation Authority in July 2000 and was based on the Lithuanian airworthiness directive CAI‑TSD-007/2000 issued in May 2000. The Lithuanian directive was prompted by the identification of a 19 mm crack found in the elevator control pulley of a Yak-52 during an inspection. The CAA of New Zealand also had an airworthiness directive (DCA/YAK/5) related to elevator bellcrank inspections based on the UK document.
The MPD 2000-004 directive was listed as a special inspection in the AWAL Yak-52 maintenance schedule, which required the bellcrank to be inspected using dye penetrant at every periodic inspection (100 flying hours or 12 months). If cracks were identified, no further flight was permitted until the bellcrank was replaced. The aircraft was inspected in accordance with MPD 2000-004 on 31 October 2018, and since then flew about 35 hours prior to the accident.
In 2009, Yakovlev issued amendment 2 of the scheduled maintenance program for the Yak-52, which extended the airframe life of the aircraft. Among the changes was the requirement for the elevator bellcrank to be inspected at intervals of 25 ± 5 flying hours, and if cracks were detected, then no further flight was permitted until the bellcrank was replaced.
As a result of the Yekaterinburg fatal accident in 2010, Yakovlev issued a letter in 2011 reiterating the requirement for dye penetrant inspections of the elevator bellcrank every 25 ± 5 flying hours, and for the aluminium alloy bellcranks to be replaced with bellcranks manufactured from 30KhGSA (30ХГСА) specification steel.
In 2012, Yakovlev issued service bulletin 121-BD (121-БД), which required all remaining aircraft with aluminium alloy bellcranks to be replaced with steel bellcranks no later than December 2012. The dye penetrant inspection interval of 25 ± 5 flying hours, as specified by amendment 2 of the Yak-52 scheduled maintenance program, remained in place for steel bellcranks.
Despite the significance of these changes in response to the accident in 2010, AWAL was not aware of these changes and therefore had not been incorporated into maintenance schedules in Australia.
Accessing airworthiness information
The Yakovlev Design Bureau provided upon request, airworthiness information such as maintenance requirements, the airframe life, and general support for Yak-52 aircraft both within Russia and overseas. Some Yak-52 aircraft, such as VH-PAE, being operated outside of Russia had reached the end of their prescribed airframe life and were no longer supported by Yakovlev. Therefore owners, operators and maintainers of these aircraft relied on local formal requirements such as MPD 2000‑004, their peers, and unofficial sources such as the internet for maintenance information.
The ATSB asked representatives from the UK CAA, CAA of New Zealand, CASA, AWAL, and maintenance organisations about their knowledge of service bulletin 121-BD. They indicated that:
The UK CAA advised the ATSB they were aware of the service bulletin and associated documents. One of which was taken as the basis for the acceptability of steel bellcranks as replacements for the original aluminium in the Yak-52s operating in the UK. They also advised that some UK operators were continuing with the inspections in MPD 2000-004 even with the steel component fitted.[19] Furthermore, they had no plans to withdraw MPD 2000-004 as there may be aircraft in the UK for which the requirements remained applicable but were updating it to align with the service bulletin, including acknowledgement of the steel replacement.
The CAA of New Zealand were unaware of the service bulletin. Prior to the issue of airworthiness directive, DCA/YAK/5 in 2012, they contacted the UK CAA and adopted the requirements of MPD 2000-004.
The Civil Aviation Safety Authority advised they were unaware of the requirements of the bulletin and there were challenges in obtaining information for Russian aircraft.
The AWAL advised they were also unaware of the requirements but would consider incorporating them into the AWAL Yak-52 maintenance schedule.
Similarly, two aircraft maintenance engineers who specialised in maintaining warbird aircraft advised they were unaware of the requirements but were aware that some Yak-52 aluminium bellcranks were being replaced with steel bellcranks.
In consideration of the minimal awareness of the service bulletin, the ATSB issued a safety advisory notice (AO-2019-027-SAN-024) on 25 November 2020. The purpose of the notice was to remind maintainers and operators of the importance of dye penetrant inspections to identify and remove defective bellcranks from service. The notice also noted that Russia, as the aircraft’s state of design, increased their inspection frequency to 25 ± 5 flying hours and that aluminium alloy bellcranks were no longer approved for use on Yak-52s operating in Russia.
Operational information
Pre-flight briefings and informed participation
Warbirds can be used for private operations provided that any passengers who are carried are given a safety briefing. Civil Aviation Safety Regulation Part 132 required a safety briefing to ensure that a person flying in the aircraft was fully informed of the risks associated with the aircraft and given the opportunity to make a properly informed decision to accept the risks.
According to the CASA advisory circular Limited category aircraft - operation (AC 132-01), all limited category aircraft were required to clearly display the word ‘limited’ on the outside near the entry to the aircraft. In addition, a further safety warning was required to be displayed in a position visible to the pilot and passenger:
WARNING
PERSONS FLY IN THIS AIRCRAFT AT THEIR OWN RISK
THIS AIRCRAFT WAS NOT DESIGNED FOR AIR TRANSPORT OPERATIONS AND IS NOT REQUIRED TO BE OPERATED TO THE SAME SAFETY STANDARDS AS AN AIRCRAFT USED FOR AIR TRANSPORT OPERATIONS
The aircraft had both these displayed in the required areas.
The basis of informed participation in Australia relies on the premise that passengers make themselves aware of the potential risks of undertaking the planned activity, are briefed on the risks, and are given ample time to consider the consequences of accepting these risks. Warbird aircraft are not designed to meet civil aviation airworthiness standards and were constructed for role specific military purposes, therefore, it is important that pilots and passengers of these aircraft are aware that they do not meet conventional airworthiness standards.
The Yak-52 flight manual also specified that a pre-flight briefing must be conducted before any passenger-carrying flight. This should include, explanation of the flight controls and instruments, fitment and operation of the harness, demonstration of the operation of the canopy, and use of the in-cockpit communications system. The second passenger confirmed that the passenger was briefed by the pilot prior to departing on harness operation, remaining clear of the flight controls, and the risk of loose articles in the cockpit. The detail included in the passenger’s briefing met the requirements of being informed.
Cost sharing
The flight was conducted under a private cost sharing arrangement, whereby operating costs for the aircraft where shared between the passenger and pilot towards the running of the aircraft for the flight. This was to be the same arrangement for the second passenger, awaiting the return of the aircraft back to Southport Airport.
Yak-52 aerobatic manoeuvring warnings
The aircraft had G load[20] limits of +7g to -5g and a never exceed speed (VNE) of 227 kt. The pilot’s operating handbook stated that all aerobatic manoeuvres ‘must be conducted at a safe height, not over built-up areas and with a pre-determined lower limit for leaving the aircraft [if a parachute is worn] if the manoeuvre cannot be recovered from’. The handbook also contained several warnings regarding specific aerobatic manoeuvres:
[Dynamic stall][21] Achieved usually through mishandling in tight turns or a too abrupt pull up. A buffet precedes the stall, and the stall is characterized by the aircraft sharply breaking to an unusual flight attitude.
All spinning must be done at a safe altitude with a predetermined bail out height…All spinning must be carried out at an altitude where recovery can be made by 1000m agl (3300 ft agl).
It is not difficult to get into a flat spin through a mishandled stall turn particularly when, as is normally the case, power is kept on. …some aircraft, after a fully developed flat spin…will NOT recover with the conventional spin recovery [techniques].
If practicing spinning, total height loss can be dramatic and even with absolutely correct recovery procedures, height loss can be in excess of 2000 ft and a bit more to level regain flight.
The manual further stated that, irrespective of how many flying hours a pilot had on other aircraft types, it was advisable to receive ‘proper instruction’ from an experienced instructor who was ‘completely familiar’ with the Yak-52, particularly in relation to flat spin recovery.
Risks associated with aerobatics
Low-level aerobatics
Conducting manoeuvres at low-level significantly increases the risk of collision with terrain if the manoeuvre is not correctly executed. For example, the Yak-52 pilot’s operating handbook indicated that greater than 2,000 ft may be required to recover from a spin. The CASA Civil Aviation Advisory Publication (CAAP) 155-1(0), Aerobatics, provided guidance on the rules relating to aerobatic flights and information about the safety risks involved when performing such operations.
As well as detailing the minimum height aerobatics shall be conducted, the CAAP also discusses the risks of low-level aerobatics. Specifically, the CAAP stated that:
Aerobatics at low-level obviously entail a higher degree of risk because of the reduced safety margins for recovery from manoeuvres. A low-level aerobatics permission should be issued not just because the holder has appropriate aerobatic skills, but because he or she has the ability to assess and manage the risks involved in low-level aerobatics, particularly the risks to third parties.
…It is highly probable that the consequence of an error or failure during low-level aerobatics will be fatal to the participants…
Physiological effects
As highlighted in CAAP 155-1(0), ‘Aerobatic manoeuvres involve rapid changes in speed and direction which impose significant accelerative forces on the aircraft and pilot. The physiological effects of these G forces can range from minor discomfort to loss of consciousness’. Such effects may include:
Grey-out: Loss of colour perception and clarity, possibly accompanied with a loss of peripheral vision during high positive G loads.
Tunnel vision: A concentric narrowing of the field of vision following grey-out.
Black-out: The field of vision narrows completely, and vision is lost.
G-induced loss of consciousness: Occurs when the blood flow to the brain, and therefore the supply of oxygen, is sufficiently reduced by the positive G forces being experienced. A high negative G for a significant period may also have a similar effect.
G incapacitation: There will be a short period of total incapacitation where the pilot is completely unconscious. This is followed by a recovery period of relative incapacitation where the pilot regains consciousness but is in a confused state and unable to control the aircraft.
Unless the aircraft has sufficient height for the pilot to reduce G, and recover vision and/or consciousness, there is a risk of collision with terrain (United States Federal Aviation Administration n.d.).
Risk perception and interventions for unsafe behaviour
Unsafe acts are an error or violation committed in the presence of a potential hazard, that if not properly controlled, could cause injury or damage (Reason 1990). Examples of unsafe acts include violations, which are deviations from practices to maintain safe operations. Research conducted by Shuch (1992) reported that pilot perception of risk may decrease with repeated successful outcomes. Shuch (1992) found that if a pilot has a history of flights without incident, then they may perceive that they have a lower likelihood of an adverse outcome based on their prior incident-free experiences.
If there are concerns about a pilot’s behaviour from a safety perspective, there are formal reporting systems available to industry people and the general public. These include:
Reporting to the local flying club or aerodrome operator.
Reporting to the ATSB using the voluntary and confidential reporting scheme (REPCON). This scheme allows any person who has an aviation safety concern to report it to the ATSB confidentially. Safety concerns include an incident or circumstance that affects or might affect the safety of aircraft operations. Once submitted, the report is de-identified to protect the reporter and forwarded to the relevant organisation that is best placed to address the issue.
Reporting unsafe behaviour to CASA using their confidential and anonymous reporting scheme. When a report is made, CASA is obliged to act on valid reported safety related information.
Similar occurrences
A search of the ATSB’s occurrence database found the following investigations relating to low‑level aerobatics.
On 5 October 2018, a BRM Aero Bristell light sport aircraft, registered VH-YVX, departed Moorabbin Airport, Victoria, with a pilot and passenger on board. The purpose of the flight was a navigation exercise in support of the pilot’s commercial pilot training requirements. Following an overfly of the intended waypoint at Stawell Airport, the aircraft was observed by witnesses to conduct a number of aerobatic‑type manoeuvres before control was lost. The pilot was unable to recover control of the aircraft before it impacted terrain. The occupants sustained significant injuries and the aircraft was destroyed.
The ATSB determined that, contrary to the aircraft’s limitations and the pilot’s qualifications, aerobatic manoeuvres were conducted during the flight, and immediately prior to the loss of control. During one of these manoeuvres, the aircraft experienced an accelerated aerodynamic stall and entered into an upright spin at an altitude of about 1,650 ft AGL, which then progressed into a fully‑developed spin. Although the pilot did not consistently apply the manufacturer’s recommended spin recovery technique, recovery from a fully‑developed spin may not have been possible in the aircraft type.
On 7 September 2018, the pilot of a Yakovlev 9-UM (YAK 9) aircraft, registered VH-YIX, departed Latrobe Airport, Victoria for a local private flight. The aircraft was observed by witnesses to the north of Moe performing aerobatic maneuvers. A short time later, the aircraft impacted the ground in a steep nose‑down attitude, fatally injuring the pilot and destroying the aircraft.
The ATSB found that the aircraft entered a spin at low altitude (below 1,000 ft) from which it was not possible to recover. There was no evidence of pilot incapacitation, or a mechanical fault with the aircraft that contributed to the accident. Although possessing an aerobatic endorsement, the pilot did not hold the endorsement to conduct aerobatics below 3,000 ft. The pilot had limited experience and recency in the YAK 9 and had not previously conducted aerobatics in the aircraft. The pilot was therefore likely unaware of its unique handling characteristics and not adequately prepared to conduct the solo aerobatic flight.
On the afternoon of 8 July 2015, the pilot of an amateur-built Pitts Model 12, registered VH‑JDZ, took off from Maitland Airport, New South Wales. Witnesses observed the aircraft at the top of what appeared to be a vertical climb. The aircraft slid backwards, tail first, before entering a horizontal spin. Shortly after, the witnesses lost sight of the aircraft below the tree line and some reported hearing a loud bang. The aircraft had collided with terrain in thick bushland. The pilot was fatally injured and the aircraft was destroyed.
Radar data and witness reports were consistent with the aircraft being used for aerobatic manoeuvres in the minutes prior to the accident, with some of the flight being conducted below 200 ft AGL. The ATSB found that, for reasons that could not be determined, VH‑JDZ entered a vertical manoeuvre from which the pilot did not regain control before colliding with terrain. The pilot had trained for aerobatics, but did not hold an aerobatic endorsement and the aircraft was being flown at a height that reduced the time available to recover from a loss of control, if required.
In the morning, the pilot and passenger departed Southport Airport, Queensland, on a private aerobatic flight in VH-PAE. During the flight, while near South Stradbroke Island, the aircraft collided with water. Both occupants sustained fatal injuries and the aircraft was destroyed.
While the aircraft in its entirety could not be located, examination of the recovered wreckage did not identify any pre-existing defects that would have contributed to the accident. Similarly, witness observations shortly before the accident suggested that there no mechanical issues with the aircraft at that time.
This analysis will examine the known events leading up to the accident, the pilot’s previous history conducting low-level aerobatic flights, and the opportunities available for aviation industry personnel to provide intervention. Further, the fatigue cracking of the elevator bellcrank, the availability of updated airworthiness information for Yak-52 aircraft operating outside Russia, and the aircraft life limits and assigned permit index will also be discussed.
Flight prior to the collision with water
The plan was to conduct a scenic flight along the coast with some aerobatics. This was consistent with witness comments, where a number of aerobatic manoeuvres was observed being conducted below 500 ft during the accident flight. In addition, Department of Defence surveillance data recorded an aircraft manoeuvring over South Stradbroke Island in a manner consistent with aerobatics and with the timing for VH-PAE. No altitude data was detected, which was consistent with the fact that the aircraft was not fitted with a transponder. However, as the aircraft was not detected by the radar numerous times, this indicated it was either below the radar coverage of three local radar sites and/or due to terrain shielding. Despite this, in the absence of recorded data or witnesses to the collision with water, it could not be determined with certainty that the pilot was conducting an aerobatic manoeuvre immediately prior to impact, but it was considered possible.
The significant amount of disruption to the aircraft, and the limited wreckage recovered, indicated the aircraft impacted the water at high speed. The damage to the right horizontal stabiliser and the vertical stabiliser suggested the aircraft entered the water inverted with its right wing down. However, in contrast, the hydraulicing found on the lower surface of the right wing suggested an upright attitude. In light of this conflicting evidence, the exact orientation of the aircraft when it collided with the water could not be determined.
However, due to the limited evidence available at the time of the accident, the ATSB was unable to consider a number of potential factors that could explain why the aircraft collided with the water. These included inadvertent passenger interference with the flight controls, loose articles interfering with the flight controls, an engine failure, partial or full pilot incapacitation possibly due to the physiological effects of conducting aerobatics, an aerodynamic stall, or otherwise mishandled manoeuvre.
Pilot’s history with low-level aerobatics
The pilot had obtained an endorsement to conduct aerobatics and spinning above 3,000 ft about 6 months prior to the accident. However, the pilot did not hold a low-level aerobatic endorsement or an operational rating for low-level flying. Despite this, witnesses and previous passengers had observed the pilot conduct aerobatics below the endorsed height, including on the accident flight. It was also noted that one of these flights had been conducted prior to the pilot receiving the endorsement. Research has shown that the perception of risk can decrease with repeated successful outcomes, which, in this case, may have reinforced the pilot’s behaviour.
In addition, while the pilot was made aware of the requirements for low-level aerobatic training by a flying instructor, the investigation found no evidence that the pilot had received any training toward this. The aerobatic endorsement process outlined in the Civil Aviation Safety Authority’s (CASA) Manual of Standards provided the means for the pilot to conduct training and be assessed for aerobatics at lower heights. If this process had been followed, the pilot would have had further opportunities to learn how to identify and manage the risks specific to low-level aerobatic manoeuvres.
As previously discussed, it could not be determined whether low-level aerobatics was being conducted at the time of the accident. Irrespective, performing these manoeuvres reduces the safety margins to recover from mishandled manoeuvres and adverse physiological effects, which substantially increases the risk of an accident.
Interventions for unsafe acts
Despite not being appropriately qualified, the pilot was observed conducting low-level aerobatics on several occasions prior to the accident by different people from within the aviation industry. While some people attempted to communicate their concerns about risk-taking behaviour to the pilot, there was no evidence found that the pilot’s behaviour had been reported to the ATSB or CASA. Direct intervention with a person observed to be engaged in unsafe flying behaviour can be challenging. For example, it can lead to defensive behaviour and an adversarial situation with a negative outcome for both parties. Therefore, confidential reporting systems such as that provided by the ATSB and CASA provide a means to escalate concerns about pilot behaviour and provide protection for the source of the report.
Elevator bellcrank fatigue crack
Examination of the elevator bellcrank found two small pre-existing fatigue cracks located adjacent to a change in thickness from the inner to the outer section of the bellcrank. The location of these cracks was coincident with the location identified in the United Kingdom Civil Aviation Authority Mandatory Permit Directive MPD 2000-004. As per the Australian Warbirds Association Limited maintenance schedule for the aircraft, which included the requirement to carry out MPD 2000-004, a dye penetrant inspection had been performed on the bellcrank about 35 hours prior to the accident. However, the ATSB was unable to determine when the cracking initiated.
While the cracking did not contribute to the accident, if it had not been identified during subsequent inspections, the crack would have eventually progressed to failure and almost certainly resulted in a loss of control.
Access to information for continued airworthiness
As some Yak-52 aircraft being operated outside of Russia had reached the end of their prescribed airframe life, they were no longer supported by Yakovlev. Therefore, the airworthiness requirements for these aircraft were determined independently by owners, operators and maintainers who relied on local formal requirements such as MPD 2000-004, their peers, and unofficial sources such as the internet for maintenance information. Consequently, these airworthiness requirements had remained relatively unchanged since 2000. This was evident from discussions with a number of relevant parties, including CASA, the Australian Warbirds Association Limited, maintainers, and operators who were not aware of service bulletin 121-BD and the preceding documentation relevant to the elevator bellcrank. In addition, it was not clearly understood that after replacing an aluminium elevator bellcrank with one manufactured from steel, the requirement for dye penetrant inspections still applied.
In accordance with the Australian airworthiness requirements at the time, the aircraft’s elevator bellcrank was inspected about 35 hours prior to the accident. The manufacturer’s most recent requirements had a shorter inspection interval, which would have resulted in the bellcrank being inspected again about 10 hours prior. However, as it could not be determined when the cracking initiated, it was unknown if the cracks would have been identified had that inspection occurred.
Despite this, not having a formal communication mechanism outside of Russia for those aircraft no longer supported, increased the risk that important information about the continued airworthiness of the Yak-52 aircraft might not be identified, which could potentially lead to in‑service failures.
Airframe life and permit index assessment
At the time the permit index assessment for VH-PAE was carried out by the Australian Warbirds Association Limited (AWAL), the aircraft was 15 years older than its prescribed airframe life of 20 years. A further 40 per cent of Yak-52s registered with AWAL had also exceeded their airframe life at the time of registration. Despite this, the aircraft, including VH-PAE, were assigned a permit index of ‘0’, which meant that they could be operated over populous areas.
While AWAL had a life extension procedure that could be applied to an aircraft that exceeded its airframe life, they did not regard the Yak-52 as having an airframe life as they had not been presented with documentation they considered suitable to define it, and from their experience they did not consider it to be an issue. However, the United Kingdom Civil Aviation Authority Mandatory Permit Directive (MPD) 1998-017 defining Yak-52 airframe life limits had been produced with the assistance of Yakovlev. Although Yak-52 aircraft in Australia were not required to comply with the airworthiness requirements of foreign authorities, the existence of an airframe life limit could be established from this directive to guide the AWAL permit index assessment.
The AWAL exposition and self-administration manual permit index assessment procedure, and if needed, the airframe life extension procedure, partly depended on the extent and quality of information provided by the aircraft owner to the approved person carrying out the assessment. However, the procedures were intended to ensure that the risk in operating warbird aircraft such as VH-PAE was confined to the occupants of the aircraft, while protecting the general public from risk of harm or property damage. By not formally considering risk elements contained within the permit index assessment, an acceptable level of safety could not be assured.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision with water involving Yakovlev Aircraft Industries Yak-52, VH-PAE, near South Stradbroke Island, Queensland, on 5 June 2019.
Contributing factors
While conducting an aerobatic flight, which included low-level manoeuvres, for reasons undetermined, the aircraft collided with the water at high speed.
Other factors that increased risk
The pilot was not trained or endorsed for low-level aerobatics but conducted them on the accident flight and previous flights. This behaviour increased the risk of an accident from either a mishandled manoeuvre or adverse physiological effects.
The pilot had previously performed unsafe acts that were witnessed by people from the aviation industry. While the pilot did receive previous warnings, there were other opportunities and means for people to formally communicate and escalate their concerns that were not used.
A pre-existing fatigue crack was found in the elevator bellcrank, which had the potential to fail in-flight and lead to a loss of control.
There was no formal mechanism for the state of design to provide airworthiness information for Yak-52 aircraft that had reached the end of their prescribed airframe life. This resulted in updated information regarding the elevator bellcrank inspection interval and design not being known or included in local maintenance schedules.
The Australian Warbirds Association Limited did not consider Yak-52 aircraft to have an airframe life, and therefore, they were assigned a permit index of zero, which allowed flight over populous areas. However, there was information available from Yakovlev via the United Kingdom Civil Aviation Authority that detailed airframe life limits.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
The initial public version of these safety issues and actions will be provided separately on the ATSB website on release of the final investigation report, to facilitate monitoring by interested parties. Where relevant, the safety issues and actions will be updated on the ATSB website after the release of the final report as further information about safety action comes to hand.
Safety action not associated with an identified safety issue
Safety advisory notice to owners and maintainers of Yak-52 aircraft
In November 2020, the Australian Transport Safety Bureau issued a safety advisory notice to owners and maintainers of Yak-52 aircraft:
Given the known fatigue cracking and potential failure of Yakovlev Aircraft Factories Yak-52 elevator bellcranks manufactured from aluminium alloy, the ATSB reminds maintainers and operators of the importance of dye penetrant inspections to remove defective bellcranks from service. The ATSB would also like to ensure that operators and maintainers of Yak-52 aircraft are aware that Russia, the aircraft’s state of design, increased the inspection frequency for the bellcranks to 25 ± 5 flying hours. Further, aluminium alloy bellcranks are no longer approved for use on Yak-52s operating in Russia.
Glossary
AGL Above Ground Level
AWAL Australian Warbirds Association Limited
CAAP Civil Aviation Advisory Publication
CAA Civil Aviation Authority
CASR Civil Aviation Safety Regulation
CASA Civil Aviation Safety Authority
MPD Mandatory Permit Directive
PI Permit index
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Federal Aviation Administration n.d. Acceleration in Aviation: G-Force. Federal Aviation Administration.
Schuch, HP 1992, The influence of flight experience on midair collision risk perception. Accident Analysis & Prevention, vol. 24, pp. 655-660.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
Civil Aviation Safety Authority
witnesses
maintenance organisation for VH-PAE
Interstate Aviation Committee (MAK)
Yakovlev Design Bureau
Department of Defence
Airservices Australia
Australian Warbirds Association Limited
Southport Flying Club
United Kingdom Air Accidents Investigation Branch
Civil Aviation Authority of New Zealand
Dutch Safety Board.
Responses were received from the:
Civil Aviation Safety Authority
Interstate Aviation Committee (MAK)
United Kingdom Air Accidents Investigation Branch
Australian Warbirds Association Limited.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Appendix
Appendix - Photographs of elevator bellcrank from the 2010 accident
Figure 8: Yak-52 elevator bellcrank from the 2010 Yekaterinburg accident
Source: Society of Independent Air Accident Investigators, modified by the ATSB
Figure 9: Fatigue fracture zones on the elevator
Note: The various zones indicate the different fatigue fracture characteristics.
Source: Society of Independent Air Accident Investigators, modified by the ATSB
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Preliminary report
Report release date: 19/07/2019
Sequence of events
On 5 June 2019, a Yakovlev Aircraft Factories Yak-52, registered VH-PAE, was conducting a private flight from Southport airfield, Queensland. The aircraft departed the airfield at about 0945 Eastern Standard Time (EST),[1] with a pilot and one passenger on board. The flight was intended to take about 30 minutes, and include a low-level scenic flight north along the coast from Broadbeach to the Jumpinpin channel area, and then seawards off Jumpinpin for some aerobatic manoeuvres, before returning to Southport airfield (Figure 1). A second passenger was waiting at the airfield to complete a similar trip once the aircraft had returned.
When the aircraft had not returned by the designated time, the second passenger became concerned and started asking members at the Southport Flying Club if they had heard anything. At about 1310, a representative from the club contacted Airservices Australia about the overdue aircraft and at 1400, the Australian Maritime Safety Authority’s Joint Rescue Coordination Centre initiated search and rescue operations. At about 1630, part of the propeller was located on the eastern side of South Stradbroke Island. In the following days, additional wreckage was also recovered from the same location, as well as the pilot and passenger, both of whom had been fatally injured.
Figure 1: Map highlighting locations of interest for the proposed flight of VH-PAE
Source: Google earth, annotated by the ATSB
Pilot information
The pilot held a current Private Pilot Licence (Aeroplane) issued on 23 May 2016. The pilot also held a Class 2 Aviation Medical Certificate that was valid until 1 May 2021. The available information from the pilot’s logbook indicated that he had about 490 hours total aeronautical experience, including 38 hours in VH-PAE. The pilot had received both a spinning and aerobatic endorsement in January 2019.
Aircraft information
The Yakovlev Aircraft Factories Yak-52 was an all-metal, two-seat, low-wing aircraft, powered by an air-cooled radial M-14P engine driving a two-bladed, variable-pitch wooden propeller. VH-PAE (Figure 2) (serial number 822001) was manufactured in 1982 and first registered with the Civil Aviation Safety Authority on 5 April 2017. The aircraft was registered to the pilot on 5 July 2018.
The most recent entry on the maintenance release was 5 days prior to the accident (on 31 May 2019) and showed that the aircraft had accumulated 1,164.2 hours’ total time‑in‑service.
Figure 2: VH-PAE
Source: Matthew Coughlin
Wreckage information
The items of wreckage recovered were taken to a secure facility by the Queensland Police Service for examination by the ATSB. These items included:
a section of the left side of the fuselage and the tail section (Figure 3)
a section of the right wing
two seat cushions
pneumatic system cylinders
a number of wooden propeller pieces.
The initial examination found that the tail of the aircraft exhibited significant damage on the vertical and right horizontal stabilisers, and it had remained attached to the fuselage by flight control cables. The significant disruption to the aircraft was indicative of a high-speed impact.
The ATSB removed a number of components from the wreckage for further examination, including various instruments from the fuselage section. The aircraft was not equipped with a flight data or cockpit voice recorder, nor was it required to be.
Figure 3: Some of the recovered pieces of VH-PAE
Source: ATSB
Ongoing investigation
The investigation is continuing and will include consideration of the following:
recovered aircraft components
aircraft maintenance documentation
pilot qualifications, experience, and medical history
weather conditions
witness observations
research and similar occurrences.
Acknowledgements
The ATSB acknowledges the support of the Queensland Police Service for their assistance during this investigation.
The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003 and is derived from the initial investigation of the occurrence. Readers are cautioned that new evidence will become available as the investigation progresses that will enhance the ATSB's understanding of the accident as outlined in this report. As such, no analysis or findings are included in this update.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 21 May 2019, while engaged in a planned cull of feral animals in Kakadu National Park, Northern Territory, a crew of three were using a Bell 206B3 JetRanger helicopter for aerial platform shooting. While the helicopter was operating at about 50 ft above the ground, the engine decelerated to idle, resulting in an immediate loss of power, and subsequent collision with terrain. The three occupants (pilot, shooter and spotter) were seriously injured.
What the ATSB found
The engine power loss was due to a leak created by a loose union on an engine reference air line. During maintenance 4 days prior to install a power turbine governor (PTG), the union, which was downstream of the work completed, had not been checked for tightness. Potentially associated with distractions in the hangar at the time, an independent inspection following installation of the PTG was probably not conducted, and document verification processes did not detect that the independent inspection had not been recorded.
The cabin was not well prepared for the subsequent collision with terrain, with a range of factors exacerbating the occupants’ injuries or increasing risk. For example, the Director of National Parks required shooters and spotters to wear helmets, but helmets were not provided or used on a routine basis. Safety issues were also identified with the ambiguous wording of the instrument permitting harness use (issued by the Civil Aviation Safety Authority), and renewal of aerial platform shooting approvals without recurrent emergency training.
Additionally, the ATSB found that the Director of National Parks did not actively manage the risk of the aerial culling task, or effectively supervise the operation. As a result, an increase in the number of crew, a change in helicopter type and change of helicopter operator all progressed without requisite risk management. This exposed crew to avoidable harm during low-level aerial shooting operations.
What has been done as a result
The operator ordered an immediate fleet wide check of the security of all flexible and rigid reference air lines in its engines. Additionally, the approved maintenance organisation improved delivery of human factors training for engineers by contracting an external provider to deliver the course.
The Civil Aviation Safety Authority (CASA) has planned action to resolve the ambiguity associated with the instrument permitting harness use, and to require operators to ensure task specialists are trained in normal and emergency procedures. In addition, the operator has taken action to ensure all crew members are aware of the risk associated with using only a harness instead of a seat belt.
The Director of National Parks (DNP) immediately suspended aerial culling activities. In December 2019, the DNP commenced an internal review of standards of practice relating to aerial culling activity and personal protective equipment, and reaffirmed its requirement for the use of helmets during any future culling activities. The DNP has also undertaken a specialist aviation safety review into its aerial culling operation and is conducting ongoing review of its risk management policy and related aspects.
Safety message
Assured airworthiness and preparation of aircraft operating at low-level is paramount. Knowing that maintenance activities carry risk of error, independent inspection is a vital risk control. Inspections must be designed and conducted in a way that will capture critical issues, and visual inspections will not always be enough.
Any organisation that requires staff to engage in high-risk aviation activities should obtain professional advice on task design, actively manage risk, and provide appropriate equipment.
The occurrence
Prior to departure
On 21 May 2019, a Bell B206B3 JetRanger helicopter, registered VH-FHW and operated by Jayrow Helicopters, was being used for an aerial (feral animal) culling task in Kakadu National Park (KNP), Northern Territory (Figure 1). The helicopter operator provided helicopters and pilots under contract to the Director of National Parks (DNP), and the other crew involved in conducting the tasks were employees of Parks Australia.
Maintenance was conducted on VH-FHW by the helicopter operator in Darwin on 16 May 2019, and the helicopter had flown 4.7 hours since that maintenance. The helicopter was repositioned to Jabiru and then Mary River Ranger Station on the afternoon of 20 May and used for aerial culling tasks.
The plan for 21 May was to use the helicopter again as an aerial platform to shoot feral animals in a prescribed area within KNP. The pilot reported that, prior to departure, they refuelled the helicopter and conducted a pre-flight inspection, and no defects were observed. The two aerial culling crew, a shooter and a spotter, both licensed aerial platform shooters and KNP rangers, loaded the helicopter with the weapons, ammunition, and supplies.
Before departure, the pilot engaged the spotter and shooter in a safety briefing. The spotter then sat in the front left seat, the pilot in the front right, and the shooter in the rear right. The pilot and spotter both wore a four-point seatbelt with upper torso restraints. The shooter wore a fall arrest harness (harness) to allow flexibility of positioning in the open doorway for the shooting task.
Figure 1: Kakadu National Park and location of accident
Source: Google Earth, annotated by the ATSB.
Accident flight
At about 0913 Central Standard Time,[1] the helicopter departed Mary River Ranger Station. The search for animals was conducted at 500 ft above ground level (AGL).
At 0923 the crew found a mob of feral horses, and the animals were mustered into a favourable location. The crew reported that this task went smoothly, and the animals were easy to manoeuvre. The mustering was conducted at about 300 ft AGL. Once the animals were in position, the crew began the culling task, and the shooting took place at about 50 ft AGL (Figure 2).
Figure 2: VH-FHW flight path
Source: Google Earth and the operator, annotated by the ATSB
At about 0957, 44 minutes into the flight, the helicopter was at a height of about 50 ft AGL over a lightly wooded area. The pilot reported that the helicopter’s engine started decelerating to idle, and the spotter recalled hearing the engine surge. The pilot’s immediate response was to ensure the throttle was fully open (which it was). The pilot quickly diagnosed the situation as a genuine emergency.
The pilot announced ‘we’re losing power and going over there’, referring to a small clearing slightly left of the nose in their direction of travel. The pilot managed the rotational energy remaining in the rotor system and the forward speed of the helicopter to reach the clearing.
The right side of the helicopter impacted a tree on the edge of the clearing, and then landed heavily in a level attitude. All three occupants were seriously injured, and the helicopter was destroyed (Figure 3).
Post-impact events
The spotter recalled, after impact, being covered in fuel and having heavily restricted movement in the neck and body. The spotter exited the helicopter and noted that the pilot and shooter were unconscious.
The spotter reported attempting to activate a handheld emergency position indicating radio beacon (EPIRB), but given that their corrective glasses were lost, the activation instructions were unable to be read. The spotter returned to the helicopter as the pilot and shooter became conscious. The pilot and spotter between them ensured the helicopter’s emergency locator transmitter (ELT) was on, and the spotter tried to make the pilot comfortable.
The spotter tried to assist the shooter in the back of the helicopter but was unable to do so. The rifle was still in the helicopter, and the barrel had punctured the floor of the cabin. The spotter made the weapon safe by removing the magazine and selecting the safety catch. The spotter located a daypack, which contained a park radio, then made a MAYDAY call which initiated the emergency response from KNP personnel.
The joint rescue coordination centre (JRCC) detected the signal from the ELT and tasked a passing Royal Australian Air Force (RAAF) C130J to search for the source. The RAAF aircraft’s crew found the wreckage of VH-FHW and directed a nearby helicopter to the scene. The crew on the second helicopter were able to provide immediate assistance. Meanwhile, the RAAF aircraft was also in communication with an inbound emergency medical service (EMS) helicopter.
The EMS helicopter arrived at the accident site about 5 minutes later. Medical professionals on board were winched from the helicopter to care for the injured personnel and prepare them for transport.
Following news of the event, the fuel supply at Jabiru was closed for testing as a precaution. This prevented the EMS helicopter from refuelling at Jabiru. Combined with limited access to site, the delays in refuelling meant extraction of the injured crew took longer than desired. The crew eventually reached hospital in Darwin at around 1900, about 9 hours after the collision with terrain.
The pilot held a valid Commercial Pilot Licence (Helicopter), and a current Class 1 Aviation Medical Certificate. Over a 40-year career, the pilot had accumulated over 18,000 hours flight time. The pilot first worked for the operator on a full-time basis in 1994, before then flying for other operators. More recently, the pilot was inducted to the operator as a contractor in 2014.
The pilot had a significant level of experience in low-level and remote area helicopter operations, including extensive experience in aerial shooting programs. The last proficiency check in single engine helicopters was conducted on 26 March 2018 (valid to 31 March 2020), and the last proficiency check for low-level helicopter operations was conducted on 1 November 2018 (valid to 1 November 2020). No problems were noted during either proficiency check.
Shooter and spotter
The shooter was a highly experienced Kakadu National Park (KNP) ranger who was first licenced for aerial platform shooting in 2002.
The spotter had over 30 years’ experience as a KNP ranger, and became a licenced aerial platform shooter in 2000.
Both the spotter and shooter had been trained in aerial platform shooting. The Civil Aviation Safety Authority (CASA) had issued permission to both personnel for carriage and discharge of a firearm from an aircraft. The conditions of permission required that, before shooting from an aerial platform, they must:
have completed training a syllabus of training by an accredited aerial platform shooting training organisation; or by the pilot in command for the type of aircraft to be used (aeroplanes or helicopters); and
retain a copy of this training course and evidence of its completion…; and
within the previous 2 years:
have conducted shooting from an aircraft; or
requalified under the training course mentioned above.
The permissions were valid for 3 years. The aerial platform shooting course was only undertaken once by both crew for the initial issue of their permissions. Permissions were then renewed by shooting from aircraft within the 2-year period. The crew also completed ground-based firearms safety courses. The spotter and shooter had not refreshed their emergency training for aerial platform shooting since the initial issue of their permissions in 2000 and 2002, respectively. They also had not conducted drills on the ground simulating a forced landing to prepare them for an actual event.
Organisational and management information
Kakadu National Park management
The Kakadu National Park (KNP) Board of Management developed, drafted, and monitored management plans for the park. The majority of land in the park was leased to the Director of National Parks (DNP) for management as a Commonwealth reserve. The KNP Board of Management worked with the DNP under a joint management framework.
The DNP was a corporate Commonwealth entity that existed under Part 19 of the Environment Protection and Biodiversity Conservation Act 1999. This entity administered, managed, and controlled the park. The DNP was supported in carrying out its functions by the Parks Australia Division of the Department of Agriculture, Water, and the Environment.
Parks Australia staff operated in the KNP as rangers under direction from the DNP and with oversight from the Board of Management.
Helicopter operator
Jayrow Helicopters held an air operator’s certificate (AOC) that authorised it to conduct a wide range of low-level aerial work activities using a wide range of helicopter types. These activities included aerial spotting and feral animal control (aerial culling).
The DNP tendered for helicopter services in late 2016 and contracted the helicopter operator to support a range of park activities under a deed of standing offer in May 2017.
The operator had provided helicopter services in remote areas of Australia for 55 years. Adaptations to the environment underpinned the expansion of its business into remote areas in the early days. Since then, its services expanded to all areas of onshore and offshore helicopter operations. The operator had a quality management system and safety management system, with a full-time safety and quality manager.
The helicopter operator’s operations in KNP were conducted from Jabiru, with management based in Darwin. The head office of the operator was in Melbourne, Victoria.
The DNP engaged aviation industry auditors to conduct second-party audits of the helicopter operator.
Approved maintenance organisation
The approved maintenance organisation was owned and operated by the same entity that operated the helicopters. The engineering manager, and the head of aircraft airworthiness and maintenance control, were based at head office in Melbourne. A senior base engineer and three full-time engineers were in place at the Darwin base. A contract engineer was temporarily employed to support a busy period of work at the time of the accident.
It was normal for most maintenance of the operator’s helicopters to take place in Darwin.
Helicopter and maintenance information
General information
VH-FHW was one of two helicopters taking part in the aerial culling program. VH-FHW was a Bell Helicopter Company 206B3 JetRanger, serial number 2838. It was manufactured in the United States in 1979, and first registered in Australia in 1980. VH-FHW had seating for a pilot and four passengers, and it was powered by one Rolls-Royce 250-C20J turboshaft engine. At the time of the accident the helicopter had accumulated about 16,916 hours total time in service (TTIS).
For the aerial shooting task, the rear right door of the helicopter was removed.
Wreckage inspection
The ATSB did not conduct an on-site examination of the wreckage. On 30 May 2019, under the guidance of the ATSB, and supervision of the Northern Territory Police, the police, Parks Australia rangers and the operator returned to the accident site to inspect the wreckage.
During the inspection of the wreckage, it was found that an engine reference air line[2] union between the power turbine governor and the accumulator was loose (Figure 4). No other pre-existing problems with the helicopter were reported to be found during the wreckage examination.
Figure 4: Loose reference air union
Source: Operator, annotated by the ATSB
Maintenance information
The helicopter underwent scheduled maintenance in Darwin on 16 May 2019, 5 days prior to the accident. At that time, the helicopter had accumulated 16,911 hours TTIS. The planned maintenance included a clean of the tail rotor assembly, a 100-hour airframe inspection, and a 150-hour engine inspection.
All planned maintenance activities were recorded in a work pack. The package was prepared in advance of the maintenance and outlined the tasks to be completed. The work was conducted by four licenced aircraft maintenance engineers over a full day. The engineers signed each element as it was completed.
During this maintenance, it became apparent that the power turbine governor (PTG) and linear actuator required replacement due to stiff operation. As the PTG change was introduced on the day of maintenance, a separate work sheet was produced for that task.
Requirements of PTG install
The PTG is designed to keep the power turbine rotating assembly in a gas turbine engine rotating at a constant speed throughout changing power demands. The PTG senses engine speed changes by sensing engine reference air pressure (from the engine compressor), and it sends a signal to the fuel control unit (FCU) to adjust the fuel flow to the engine accordingly. A linear actuator assists the PTG by linking it to the pilot’s controls, allowing the PTG to adapt to changing power demands more efficiently.
The maintenance instructions for the replacement of the PTG included a warning in relation to the installation (Figure 5). The engine manufacturer (Rolls-Royce) advised that this warning was repeated throughout its 250-C20 Series Operation and Maintenance manual and applied to all union connections. This included both ends of all lines installed on the PTG. A loose union could create a leak, which would in turn cause engine power loss.
Figure 5: PTG installation warning
Source: Rolls-Royce 250-C20 Series Operation and Maintenance Manual
Replacing the PTG requires removing the air carrying flexible hose and pipes from the old unit and replacing them on the new unit. It is normal practice in maintenance to disconnect the PTG and loosen the other end of the lines (such as the engine reference air line) to allow manipulation of the lines for removal and refitting.
Replacement of the PTG on VH-FHW
The maintenance engineer that conducted the PTG replacement was a licenced aircraft maintenance engineer (LAME) with 27 years’ experience in Australia and overseas. They had maintained the operator’s fleet at the remote base in Darwin for 4 years.
The engineer stated that it was not necessary to loosen the other end of the flexible engine reference air line when replacing the PTG and that the reference air line adjacent to the accumulator was not touched at any point during the maintenance on 16 May 2019.
Other recent activities that could have loosened or dislodged the reference air line union were a turbine module change on 3 July 2015, a compressor module change on 6 July 2015, and a PTG change on 3 May 2018.
Human factors in engineering
The approved maintenance organisation had self-paced human factors training material for its engineers. The LAME that conducted the PTG replacement on 16 May 2019 completed that training on 12 January 2016.
In a Civil Aviation Safety Authority (CASA) published guide (Safety behaviours: human factors for engineers), the stated average rate of leaving a loose nut during maintenance was one in 250. The guide stated that such lapses were most commonly encountered when a distraction was introduced to the maintenance task.
The engineer that replaced the PTG stated that distraction and interruption were existent at the engineering facility where the maintenance was conducted. Such interruptions were witnessed by ATSB investigators during the course of the investigation.
Independent inspection requirements
Civil Aviation Regulation (CAR) part 42G (Flight control systems: additional requirements), mandated that an aircraft’s flight controls required independent inspection following maintenance activities. No other systems were required by regulation to undergo independent inspection. The qualification requirements of people conducting independent inspections were detailed in schedule 8 of CAR 42ZC (Maintenance on Australian aircraft in Australian territory). The qualified parties were essentially licenced engineers and pilots.
The maintenance organisation’s Engineering Procedures & Control Manual allowed appropriate persons to conduct independent inspections as per CAR 42G. It stated that the certifying LAME was responsible for ensuring the person conducting the independent inspection was qualified, trained, and briefed. It was the engineer’s responsibility to brief the pilots, and train them to conduct the independent inspections required. This was managed on an as needed basis without standardisation or formal support.
As human factors principals have been increasingly applied to the practice of aircraft maintenance over the years, the aviation industry has recognised the benefit of expanding the use of independent inspections beyond flight controls. Accordingly, many maintenance organisations have increased independent inspection requirements beyond the regulatory requirements to all critical maintenance tasks. Additionally, the Flight Safety Foundation’s voluntarily adopted Basic Aviation Risk Standard (BARS) required registered operators (of that standard) to identify critical maintenance tasks (CMT), and stated:
Maintenance tasks that involve assembly or disturbance of any system that may affect the flight path, attitude or propulsive force, which, if errors occurred, could result in a failure, malfunction, or defect that would endanger the safe operation of the aircraft must be considered as a CMT.
The maintenance organisation’s Engineering Procedures & Control Manual, last updated 10 January 2018 and valid at the time of the accident, stated that ‘second inspection’ requirements were added to the manual on 7 October 2008. The manual specified additional independent inspection requirements over and above the requirements of CAR 42G. These included:
Main rotor, tail rotor systems and drive-train components.
All powerplant controls, including MFCUs, AFCUs, FCUs, EECUs, etc
All powerplant electrical connectors
All closed areas prior to refitment of panels/assemblies/components, etc.
Fluid line fittings.
Note: Whether the complete system or only part of a system has been disturbed, the independent inspectors should thoroughly check the system and adjacent areas, ensuring that all tools, equipment and materials have been accounted for and removed.
Independent inspection of maintenance on 16 May 2019
The work pack generated at the time of maintenance on 16 May 2019 carried space for signing off after independent inspection of critical maintenance tasks. Two tasks relating to the reassembly of the tail rotor pitch control were identified for independent inspection. These items were signed as carried out by the LAME who completed the work and signed as inspected by a second LAME.
There was no documentary evidence to show independent inspection of the PTG install had taken place. The LAME that conducted the task stated that a pilot had conducted a visual inspection of the installation, and that due to distraction from unrelated operational demands the signing of the paperwork was missed.
The pilot who was nominated as having done the inspection stated that they had done duplicate inspections at times for the engineers, but it was not a common occurrence. They could not recall conducting a visual inspection of the PTG installation or any other aspect of VH-FHW during its maintenance on 16 May.
Verification of maintenance activities
The logbooks for all aircraft were held at head office in Melbourne. All maintenance documentation from the Darwin base was sent to Melbourne for verification prior to a maintenance release being issued for an aircraft. Following the maintenance on 16 May 2019, a maintenance release was issued for VH-FHW without the required independent inspection requirement being signed as completed for the PTG installation.
The last audit commission by the DNP on the helicopter operator and its maintenance organisation in September 2018 included the following observation:
An inspection of a recent work pack for the last service completed for (a company helicopter) showed records to be completed thoroughly and correctly. Logbooks are not kept on site and all records are scanned and sent electronically to the head office. (The operator) meet(s) the requirements of … the Deed of Standing Offer.
Torque seal
As a visual indicator of alignment, and an aid to indicate when an item has been secured, aircraft engineers often applied torque seal to that item. Pilots conducting visual inspections in the field could check the torque seal for cracks or movement. A crack or movement could indicate that the item was potentially not secure (Figure 6). However, torque seal is a hard lacquer and is not a perfect indicator. It can flake and crack due to heat or exposure to the elements (potentially providing false indications of movement), or if there is only slight movement it may only indicate hard to detect hairline cracks.
Orange torque seal had been applied to the several areas around the PTG, and these areas corresponded to the parts the engineer stated were manipulated when installing the PTG (Figure 6). There was yellow torque seal applied where the loose reference air line was located and it was observed to be cracked following the accident (Figure 6). Yellow torque seal was also present on some other parts that were not manipulated during the last maintenance.
Figure 6: Torque seal on air line unions as found on VH-FHW
Source: Operator, annotated by the ATSB
Subsequent inspections of the helicopter
Pilot inspections involved a visual check of the unions at the end of the air lines in the engine compartment, including the condition of the torque seal on air lines in-line with the PTG. However, the PTG lines were one of many components to inspect that would have torque seal applied (that is, there could be dozens of items with torque seal applied that needed to be checked during a daily inspection or similar pilot inspection).
Several visual inspections were made of VH-FHW by qualified people in the normal course of operation following the 16 May 2019 maintenance and none identified any defect. More specifically:
On 17 May 2019, after the scheduled maintenance and replacement of the PTG had been conducted, a functional check of the helicopter’s engine and aircraft was conducted on the tarmac at the operator’s Darwin base. Inspection was required before the helicopter was operated, and was also done during the ground run. No defects were reported.
On the morning of 20 May 2019, VH-FHW was flown to Jabiru and then used on a stream sampling job nearby. The pilot who conducted these flights reported that the daily inspection of the helicopter identified no defects and that the helicopter performed well.
On the afternoon of 20 May 2019, the helicopter was left in Jabiru for the pilot contracted for the aerial culling task to collect. That pilot inspected VH-FHW before departing Jabiru for Mary River Ranger Station and stated that the helicopter presented no defects. The afternoon was spent using the helicopter for aerial culling tasks. The pilot reported that the check conducted at the end of the day identified no issues.
On the morning of 21 May 2019, the pilot reported having ample light and time to conduct a thorough daily inspection. The pilot stated that the daily inspection was conducted, and no defects were identified.
Emergency procedures
Regarding the Rolls-Royce 250-C20J engine, if the PTG fails on the high side (high RPM), and puts too much fuel into the engine, the engine will overspeed. The pilot can decrease the throttle to reduce the fuel flow and therefore manage RPM.
As in the case of the accident on 21 March 2019, if the PTG fails on the low side (low RPM), and restricts the amount of fuel going to the engine, there is no adjustment the pilot can make to increase the fuel flow for this engine type. The pilot must instead treat the problem like an engine failure. When operating at a low height above ground, this means controlling rotor RPM with collective pitch and cyclic and managing the helicopter for the best available outcome.
Meteorological conditions
The pilot reported that there was limited internet connectivity at the Mary River Roadhouse so was unable to obtain updated weather information online. The pilot was familiar with the area and, given the conditions, they were satisfied that the weather was suitable for the planned flight.
The Bureau of Meteorology (BoM) provided automated weather reports for Jabiru for the morning of 21 May 2019. The reports indicated an east to north-easterly wind at 12 kt, nil cloud, temperatures from 28 °C to 30 °C, and visibility greater than 10 km. The weather was typical for the Northern Territory dry season and conducive to flying.
Cabin safety information
Occupant injuries
All three occupants of VH-FHW received serious injuries. The pilot received serious back and foot injuries, as well as chemical burns to the body from leaked fuel. The spotter received a serious back injury, a gash to the outside of the lower right leg, and damage to the right arm. The shooter received chemical burns from fuel, and serious injuries to the back, right hip, and scalp.
Seatbelts and harness
VH-FHW was fitted with four-point seatbelts with upper torso restraints (UTRs) in all seating positions. For the KNP shooting operations in B206B3 JetRanger helicopters, the pilot and the spotter both wore the four-point aircraft seatbelts.
The helicopter operator provided a harness for the shooter, which the shooter did not use. For reasons of comfort, the shooter instead used a harness supplied by Parks Australia, attached by way of a non-energy absorbing, webbing restraint strap of around 1 m to a specified anchor point.
The harness’s design complied with ATSO-C1003[3] and was a quick release type, that could be released under load using two distinct movements (Figure 7), and it was approved under Civil Aviation Safety Regulation (CASR) 21 (Certification and airworthiness requirements for aircraft and parts). It was attached to the aircraft with an adjustable strap. Figure 8 shows the location of the anchor point installation in VH-FHW, which was approved by an authorised engineer under CAR 35 (Approval of design of modification or repair). The anchor point design required it to be installed on the left side of the cabin for use at the rear right door.
Both the shooter’s harness and the anchor point in VH-FHW carried a caveat. Figure 9 shows the harness manufacturer’s statement:
Not approved for take off or landing.
Additionally, the flight manual supplement for the approved anchor point stated:
The camera person/hoist operator must be restrained by his standard seat belt for take-off and landing.
The harness used by the shooter did not fail in the accident sequence, though it was noted after the accident to be past its 10-year retirement date by 3 weeks (Figure 7). The operator took immediate steps to prevent third parties using expired equipment aboard their aircraft after discovering this post-accident.
Harnesses are commonly worn in many aircraft applications. They are designed to prevent people from falling within, and from, the aircraft. They are not designed to protect the occupant during a collision or impact sequence.
Figure 7: Shooter’s harness, rear view
Source: Northern Territory Police, annotated by the ATSB
Figure 8: Harness anchor point
Source: Operator, annotated by the ATSB
Brace positions and emergency response
The operator specified brace positions for passengers in seats fitted with a lap belt and for seats fitted with a lap belt and UTR (Figure 9).
During the occurrence, the seatbelt with UTR kept the pilot in place while they flew the aircraft for as long as they could to achieve the best outcome.
Although the spotter was aware of the brace position, and the UTR held the spotter in their seat, they reported that they lifted their legs prior to impact. In contrast, the specified brace position required the occupant’s feet to be flat on the floor, as depicted in Figure 9.
Figure 9: Brace position information provided by operator
Source: Operator via the Director of National Parks
There was no universally recommended brace position for a crew member in a fall arrest harness, and the operator had not provided procedures or guidance for a brace position for a shooter wearing only a harness. The shooter reported that they crouched down as much as possible, as if they were wearing a lap belt.
A document on helicopter ditching produced by the North Atlantic Treaty Organisation (NATO) in 1989 recommended:
Those unrestrained or on a long tethered harness prior to impact, should if at all possible strap into the nearest seat and assume (a standard brace position). Otherwise they should immediately lie face down flat on the floor with their heads buried in the crook of their arms.
Those actions require time and space, which may not be available when responding to an emergency at a low height above the ground in a small helicopter.
Reducing the flail envelope of an occupant is a vital part of reducing harm in an impact sequence. Even short single-point restraints have been demonstrated to allow significant flail injury to occupants (see for example AO-2014-053). Figure 10 shows the estimated flail envelopes for the occupants of VH-FHW at the time of the accident. The shooter, with a single-point restraint, had a much larger flail envelope than the two front seat occupants.
In the event of an emergency (such as an impending impact), the shooter was required to throw their weapon out of the exit. The shooter advised that they understood this requirement. However, on this occasion they brought the live rifle into the cabin and pointed the barrel down.
Figure 10: Estimated flail envelope for occupants of VH-FHW
Source: ATSB
Harness use instrument
The use of seatbelts is mandated in CAR 251 (Seat belts and safety harness). It stated:
Subject to this regulation, seat belts shall be worn by all crew members and passengers:
during take-off and landing…
when the aircraft is flying at a height of less than 1,000 feet above the terrain…
CASA may direct that a type of safety harness specified in the direction shall be worn in place of a seat belt in the circumstances set out in the direction…
Civil Aviation Order (CAO) 20.16.3 (Air service operations – carriage of persons) detailed technical requirements to support CAR 251. It stated:
3.1 Each crew member and each passenger shall occupy a seat of an approved type:
(a) during take-off and landing; and …
(c) when the aircraft is flying at a height less than 1000 feet above the terrain; ….
4.1 … safety harnesses, or seat belts where safety harnesses are not fitted, shall be worn by all persons at the times listed in paragraph 3.1…
Airworthiness bulletin (AWB) 25-007 issue 3 (Personnel Harnesses, Restraint Straps and Approved Attachment Points) alerted operators to safety issues surrounding the use of harnesses. The AWB did not offer guidance with respect to a brace position for personnel wearing only a harness.
In November 2018, CASA issued the instrument CASA.EQUIP.0029 under CAR 251(3) to the helicopter operator, exempting the operator from CAR 251(1) when certain conditions were met. It stated:
… approved safety harnesses may be worn in lieu of seat belts in a helicopter during take-off and landing and when the helicopter is flying at a height less than 1,000 feet above the terrain.
The instrument also specified various conditions and requirements, which included:
General conditions
The direction to use the harness is applicable only to the conduct of those tasks where the assistance of the otherwise unrestrained crew member is vital to the operational safety or to the conduct of specific aerial work functions as detailed in the operator's operations manual…
The harness must be worn in place of the seat belt for the minimum time commensurate with flight safety;…
Procedures, drills, operating crew duties and recency requirements covering both normal and emergency operations whilst wearing a safety harness, or swapping between seat belt and safety harness, must be defined and published in the operator's operations manual…
Crew requirements
Before flight, the pilot in command must brief crew members in regard to the responsibilities applicable to both normal and emergency operations whilst wearing a safety harness or swapping between seat belt and safety harness. The briefing must include the procedures to be adopted to afford the best protection to crewmembers in the event of a forced landing…
Conduct of flight
An approved seat and seat belt, for use in an emergency, must be available at all times to the occupant of the safety harness…
Transfer between a seat belt and a safety harness during flight must only occur above 1,000 feet AGL, where practicable, and with the cabin doors closed. These restrictions apply only if the occupant is not secured by either system during the transfer…
Notwithstanding the requirements of [previous paragraph], the occupant must not be secured by more than one (1) restraint system for other than the actual transfer (Ref CAO 108.42 para 3.6) except during the conduct of specific power line aerial work functions as detailed in the operator's operations manual.
Operator's responsibilities
…The Operator must further ensure that any person wearing a safety harness pursuant to the provisions of this direction is fully apprised as to the inherent limitations and potential risks involved in the use of such a harness, when it is worn in place of a seat belt or other restraining device of a type that would otherwise be required in accordance with the provisions of CAR 251.
This instrument was a common exemption to seatbelt requirements for operators conducting aerial work in Australia. Jayrow Helicopter’s instrument was initially issued in 2004.
CASA informed the ATSB that, despite the wording of the instrument, caveats on the specific equipment used (see Seatbelts and harness ), and conditions of the instrument requiring equipment to be approved for take-off and landing, meant that a harness could not be worn in lieu of seatbelts during take-off and landing. CASA also stated that, while the wording appeared otherwise, the instrument was never intended to allow the use of a harness during take-off and landing instead of a seatbelt.
CASA advised that no risk analysis had taken place regarding the potential use of the harness instead of a seatbelt for take-off and landing when issuing this instrument, as it had not anticipated that the instrument could be interpreted that way.
CASA provided renewals of the operator’s instrument every 3 years. Renewals relied on the existence of an antecedent instrument, and upon the content of the operator’s operations manual providing the means to fulfil the conditions of the instrument.
Harness use below 1,000 ft
There were three distinct phases of flight mentioned in CAR 251 and instrument CASA.EQUIP.0029: take-off, landing, and flight below 1,000 ft. The use of a harness below 1,000 ft was essential for completion of the shooting task, and the operator had published aerial culling procedures and harness use procedures in its operations manual. The harness use procedures included:
annual recertification of equipment
visual inspection of harness and anchor point
pilot briefing on use by senior base pilot
instructions on proper assembly of the quick release mechanism.
The helicopter operator stated that all crew involved in the shooting tasks had received a mass brief at the beginning of the aerial culling program, and regular briefings before flights at the aircraft. The manager in Darwin advised that the mass brief included the use of the harness, operation of the quick release, and shooting procedures as well as normal flying operations. The pilot reported that the pre-flight briefings at the aircraft included avoidance of rotating parts, how seatbelts and doors worked, and location of emergency equipment, as well as task-specific points such as coordination of turning with shooting.
Parks Australia staff members reported that, aside from the method of attachment and release from the harness, there was no other guidance or information provided to the aerial culling personnel about precautions or risks when utilising the harness, with or without the aircraft seatbelt fitted.
As noted above, the CASA instrument required a person wearing a harness to be made aware of the increased level of risk they are assuming when wearing a harness and not wearing a seatbelt. Parks Australia staff members stated they did not feel this was sufficiently communicated to them.
Harness use on take-off and landing
The pilot recalled that, on the day of the accident, the shooter was wearing only the harness on departure from the ranger station. The pilot reported a preference for crew to use the seatbelt, and on this occasion allowed the shooter to use the harness for comfort.
The shooter recalled wearing the seatbelt (lap belt) over the harness during the take-off and throughout the flight. Following the accident, the shooter was found to be only wearing the harness.
Interviews with the operator’s personnel and Parks Australia staff members confirmed that, in the B206B3, shooters would usually remain in the harness attached to the helicopter with the restraint strap at all stages of flight. Flight crew and Parks Australia personnel also reported that, if the aircraft seatbelt was used, it was normal to use the lap belt portion of the seatbelt in addition to the safety harness.
As noted above, the CASA instrument stated that the occupant must not be secured by more than one restraint system for other than the transfer between restraints.[4]
Ancillary radio install
In 2015 an ancillary radio system was installed in the front passenger footwell of VH-FHW, in accordance with a CAR 35 engineering order. The installation protruded about 8 cm into the footwell (Figure 11). The radio system was a marine VHF/UHF radio, and it was not required for the aerial culling tasks. It had sharp small radii corners, and was not padded.
The spotter reported that the ancillary radio’s placement made it difficult to use the push-to-talk foot switch for the intercom system. Additionally, the large laceration to the spotter’s right leg matched the small radius, metal corners and edges of the ancillary radio installation.
VH-FHW, serial number 2838, was a Bell 206B manufactured in 1979. The Bell 206B model was certified in the normal category in 1971, and its certification basis was the US Civil Aviation Regulation 6, dated December 1956, with various amendments. In terms of emergency landing conditions, that design standard stated:
The structure shall be designed to give every reasonable probability that all of the occupants, if they make proper use of the seats, belts, and other provisions…will escape serious injury in the event of a minor crash landing In which the occupants experience the following ultimate inertia forces… Upward 1.5g (downward 4.0g)…Forward 4.0g… Sideward 2.0g.…
Consequently, modifications to the aircraft (such as for the radio installation in VH-FHW) needed only to comply with the original design standard.
From 1989, the US Federal Aviation Regulation (FAR) 27.561 requirement for helicopter types certified in the normal category were required to be designed to protect up to 16 g forward, 20 g downward, 8g sideward and 4 g upward. From 1984, FAR 27.785 also required that:
Each seat, safety belt, harness, and adjacent part of the rotorcraft at each station designated for occupancy during take-off and landing must be free of potentially injurious objects, sharp edges, protuberances, and hard surfaces and must be designed so that a person making proper use of these facilities will not suffer serious injury in an emergency landing…
The Bell 206B3 is piloted from the right seat, however dual controls can be made available for pilot training and proficiency checks. This would require an instructor or check pilot to fly the helicopter from the left seat. US CAR 6 also required that:
…the pilot will be able to perform all of his duties and operate the controls in the correct manner…
The pedals at the front left seat of VH-FHW were disconnected from the flight control system. That position can be equipped with flight controls for tasks that require two pilots. The protrusion of the radio installation in VH-FHW over the pedals would likely prevent a pilot from effectively operating the controls. The engineering order for the installation did not prohibit a second pilot from flying the aircraft from the left seat.
Figure 11: Exemplar radio installation showing approximate position in footwell
Source: Maintenance organisation, annotated by the ATSB
The aerial culling task
Low-level operations
Helicopters are used extensively in low-level operations to support numerous industries in Australia. These notably include emergency services, fire suppression, and management of national parks. Low-level operation is defined as any operation below 500 ft, aside from take-off and landing.
Low-level flight brings several significant complexities to the operation, and pilots require training and approval to operate helicopters at low-level. One such complexity is management of forced landings. Both time and availability of suitable forced landing areas are significantly reduced.
During a forced landing, a helicopter can descend at around 2,000 ft/minute. From 1,000 ft, this provides around 30 seconds for preparation of the cabin for a forced landing. From 50 ft, the time is reduced to a few seconds, leaving very little (if any) effective time for warning or preparation.
Low-level flight also vastly reduces the availability of forced landing sites (Figure 12) At best glide speed (69 kt in a B206B3), a glide ratio of around 4:1 is achievable. Low-level work ordinarily occurs at lower speeds than that, and in aerial culling the pilot must match the speed of the animals, further reducing choice of forced landing areas.
Figure 12: Theoretical choice of forced landing area at best glide speed
Source: ATSB
Task design
The primary purpose of the aerial culling activity was to care for Country and protect the habitat and people in the park from damage caused by feral animals.
It was normal practice across industry that an aerial culling task was performed with just two people on board the helicopter: a pilot and a shooter. For example, the successful brucellosis and tuberculosis eradication campaign in Australia ran for 27 years and made extensive use of aerial culling with two crew. In addition, the Northern Territory government’s aerial platform shooting course guide, under which the Parks Australia shooters were trained, did not mention observers or spotters being on board an aircraft.
The pilot of VH-FHW, who had 30 years’ experience in aerial culling, had ordinarily conducted shooting tasks with just two people on board. Experienced aerial shooters interviewed after the accident also stated a preference for carrying just the pilot and shooter on board to reduce risk to crew, carry more fuel to improve endurance, and do more work.
Parks Australia employees advised that aerial culling tasks in KNP were conducted in Robinson R44 aircraft with just a pilot and shooter up until 2016. In 2017, the DNP switched to a different helicopter operator, which provided a range of services using the larger Bell 206 JetRanger and Airbus Helicopters EC120B aircraft.
The DNP used the higher capacity of the larger helicopter to include the spotter position and improve data collection (in terms of information about the species, number and location of kills). A Parks Australia representative stated that it was critical that the spotter was carried for the success of the shoot, and to counter the risk of not having data for stakeholders. Accordingly, since 2017, the DNP designed the aerial culling task for three people. It required a spotter on board the helicopter in addition to the shooter and the pilot. Prior to 2017, when using the R44 helicopter, data collection was performed by the shooter.
Safe operating procedures
The DNP amended its safe operating procedures (SOPs) issued for aerial platform shooting in November 2016. The procedures included information relevant for conducting the task in an R44 and in a JetRanger and rated the risk to crews as high. For example, the SOPs accommodated the inclusion of the spotter (only relevant to a JetRanger), and required the shooter to wear a seatbelt at all times (which was applicable to the R44 but not how the operation was conducted in a JetRanger).
The SOPs required the spotter to have training in:
map reading and navigation
aerial animal welfare assessment
locating the animals and counting kills from a helicopter.
During shooting, the pilot positioned the helicopter to the left of the mob of horses, and matched the speed and track of the helicopter to that of the animals. In a JetRanger, the spotter (seated in the front left seat) could not see what was happening on the right side of the helicopter where the shooting was taking place. The spotter would therefore require the input of the pilot and shooter to conduct the count (Figure 13).
Figure 13: Estimated firing zone and visibility
Source: ATSB
The SOPs also stated that safety equipment for the task included a flight helmet with intercom. No flight helmets were provided to the aerial shooting crew. The shooter and spotter on the accident flight reported that they were not wearing helmets and did not generally wear helmets during shooting operations. The pilot provided and wore their own helmet.
The spotter reported that they wore a headset for communicating with the pilot and shooter. The shooter reported that they also wore a headset but pushed it back when shooting, so that the earcups would not interfere with manipulation and aiming of the rifle.
Oversight of contracted helicopter operator
On award of the contract for helicopter services, and annually thereafter, the DNP commissioned an independent aviation auditing company to conduct an audit of the helicopter operator and its co-owned maintenance organisation. The audit examined the operator’s ability to provide the service while observing aviation regulations, as well as observing the terms of the contract entered into between the parties.
An audit conducted in September 2018 resulted in three findings, two related to sling load equipment and aircraft parking, and a third due to the operator’s emergency response plan at Jabiru not including relevant emergency contact details. The operator added the emergency contacts to its emergency response plan at the time of audit.
Oversight of shooting operations
There was limited oversight of shooting operations by the DNP. The aircraft travel plan was a document relied on by the park manager and aerial culling team for authorisation of the task, and it was detailed in the DNP aircraft safety policy as being ‘a very important safety factor’. This document was required to be completed for each task, but the template had not been updated since the change in helicopter operator in late 2016. It carried emergency contact details of the previous helicopter operator, and no contact details for the current helicopter operator.
A Parks Australia representative stated that they did not have visibility of the aerial platform shooting management process and that high turnover in the management role over the preceding years had hampered Parks Australia’s ability to provide oversight in that regard. The culling team had no permanent manager in place. A manager was temporarily seconded to the team to help prepare for the culling task in the lead up to the current program, yet risk management documentation for the operation, which was to be completed at manager level, was not conducted and had last been addressed in 2015.
This situation was accepted by management because the crew were all licenced, and local debriefs took place to manage the risk. However, the SOPs did not require a debrief after shooting and there was no record of crew debriefs, no indication of what the content should be, and no internal procedures to verify they were taking place.
Risk management
The date of the DNP’s last risk assessment for aerial culling was 3 August 2015, with a stated duration of 12 months. Since that time, a number of aerial culling tasks had taken place. In addition, the helicopter operator, helicopter type, crew configuration, and SOPs had all changed.
The introduction of a new helicopter operator introduced changes to elements such as:
the integration of the standard operating procedures of the operator and the DNP’s SOPs
task management documentation (trip plan details for example)
emergency response planning
emergency contacts.
The helicopter type had changed from an R44 to B206B3s (JetRangers) and EC120B helicopters. This introduced changes to the:
seating position of the shooter
shooting position of the shooter
restraints used by the shooter (fall restraint harness in JetRanger instead of a seatbelt in R44)
management of role equipment
inclusion of the spotter.
The inclusion of the spotter introduced changes to:
available fuel load
number of people exposed to low-level helicopter operations.
None of these changes had been formally analysed by the DNP for their effect on the risk assessment, and the risk assessment as it stood was not equipped to capture the changes. Additionally, the risk assessment did not discuss protection of the crew through provision of personal protective equipment. Also, there was no formal risk analysis of the inclusion of the spotter position, or consideration of the potential benefits of improved data collection when weighed against operational difficulties in recording data, reduced efficiencies in operation, and increased exposure of employees to risk.
Additionally, the park’s radio network was cited as a mitigator for:
injury to person on ground from stray bullet or ricochet
inappropriate storage or transport of firearms
incursion of people on ground into the shooting area.
However, KNP personnel reported that the park’s radio was only available 10 per cent of the time to the crew in flight, and the radio network was reported by a Parks Australia representative to be in need of maintenance and upgrade, yet upgrade required resources they did not have. If the aerial culling crew on a helicopter needed to talk to their ground support personnel, they had to land by the road to talk face-to-face. The risk management plan did not document these limitations with the mitigator or identify treatments to address the situation.
While the helicopter was operating at about 50 ft above the ground for the aerial culling task, the engine lost power and the pilot was required to conduct an emergency landing with limited options available. As a result of the collision with terrain, the three occupants (pilot, shooter and spotter) were seriously injured.
This analysis will initially discuss the factors associated with the engine power loss, including the loose reference air line and the associated inspections of this component. It will then discuss various factors that increased the risk of injury to occupants, including the preparation of aircraft for low-level operations, and design and management of the low-level aerial culling task.
Loss of engine power
Based on the available evidence, the direct initiator of the engine power loss was the loose reference air line connected to the accumulator downstream from the power turbine governor (PTG). The reference air union was found loose at the accident site, and it was considered very unlikely that this would have loosened during the impact sequence.
In addition, a loose reference air union is consistent with the descriptions of the engine power loss. It would have vented air pressure from between the PTG and the fuel control unit, which the fuel control unit recognised as a signal to reduce fuel flow to idle. Reducing fuel flow to idle would have decreased the power generated by the engine.
In summary, the ATSB concluded that the loose union on the engine reference air line unscrewed in flight, creating a leak, and this leak resulted in a loss of engine power.
There was no manual override for a low-side governor failure available to the pilot. Therefore, the reduction in engine power deprived the pilot of the power required to keep the helicopter airborne, leading to the forced landing and collision with terrain.
It is virtually certain that the union at the accumulator end of the flexible hose from the PTG would stay fastened if the attachment points were serviceable and the nut was sufficiently torqued. A failure of the attachment point would result in a crack in the hose end fitting, and no cracks were reported. Therefore, it is extremely likely that the nut was loosened at some point and not correctly retightened. It could not be definitively determined when this occurred.
The PTG was replaced on 16 May 2019, 5 days (and 4.7 flight hours) prior to the accident. The engineer who replaced the PTG reported that the engine reference air line union was not manipulated during that maintenance. They stated it was not necessary to do so, as the flexible hose could be manoeuvred at the PTG end. Regardless of whether it was intended, it is possible that the union loosened while the engineer manoeuvred the PTG end of the hose.
The warning in the PTG installation documentation, regarding tightening of fittings and tubes, meant that all lines and unions at both ends should have been checked for tightness. As the hose-to-accumulator union was not touched, it was not intentionally loosened, yet neither was it physically checked for tightness. It is likely that such a check at that time would have identified the loose union.
Maintenance, inspection, and verification
There were three opportunities for the loose air line union to be detected before release to service:
the engineer’s own verification of the PTG installation
independent inspection by another person
verification of completeness of the relevant documentation.
Secondary checks by installing engineers and independent inspection by other trained parties are designed to catch lapses as part of an error-tolerant system. It is common practice for engineers to double check the tightness of unions to verify their own work. It is, however, notoriously difficult to detect issues in your own work (Sarter and Alexander 2000), and research has shown that errors of omission relating to fastenings are particularly difficult to detect (Reason and Hobbs 2003).
As already noted, the engineer that conducted the PTG replacement stated that the other end of the flexible hose was not touched. As such, self-verification of the installation concentrated on the PTG end of the flexible hose and the rigid pipes. It is noted that none of the unions on the PTG end loosened.
Given the likelihood of errors during procedural tasks such as maintenance, an independent inspection is a major part of capturing problems. Accordingly, the maintenance organisation’s procedures required independent inspections to be conducted for a range of activities in addition to the minimum regulatory requirements, including for fluid line fittings. In this case however, the independent inspection probably did not occur. The engineer and pilot provided differing accounts of the conduct of the inspection, and there was no paperwork to verify it had taken place.
Even if the independent inspection occurred, it is not certain that it would have identified the problem. The inspection specified was visual, and the only way to detect the loose union would be to demonstrate tightness of all unions, including unions downstream of the PTG. Tightness can only be assured by placing a spanner on the union and checking it for tightness during independent inspection. Accordingly, a thorough, well-designed independent inspection at the time of maintenance is vital in ensuring the continued airworthiness of an aircraft.
Verification of completeness of paperwork is an opportunity to detect tasks or activities that were potentially missed. Following that step, the issuance of a maintenance release is a trusted signal to all parties that the maintenance was carried out as required and that the aircraft is airworthy.
In this case, the independent inspection documentation was supplied as part of the work package, however, being a separate sheet, it may have been overlooked in the review. On this occasion, the verification of the documents did not detect that the independent inspection of the PTG installation had not been signed. As a result, a maintenance release was issued, and the aircraft was returned to service without full assurance of continued airworthiness.
Torque seal, such as was present on the engine reference air line union, would ordinarily be applied after independent inspection and demonstration of tightness. In this case, torque seal had been applied to the air line union, and it was cracked. However, the torque seal was consistent with that used on a maintenance task prior to 16 May 2019, and not consistent with the torque seal applied during the 16 May 2019 PTG replacement task.
The exact meaning of this evidence is not clear, and a range of possibilities exist. In particular:
torque seal was applied to a loose union an at undetermined time
torque seal was correctly applied to a tight union that was later loosened.
If the torque seal had been applied to a loose union, this would have potentially obscured a missed step in tightening the union. However, if the loose union existed prior to the 16 May 2019, it seems unclear why it would have taken so long to manifest into a leak.
Regardless of when the torque seal was applied, cracks in the torque seal were not identified during the 16 May 2019 maintenance or on other occasions. This could also be due to a variety of reasons, including:
the torque seal was cracked but the crack was not readily detectable
the torque seal was noticeably cracked but missed by all who later inspected the aircraft.
Following maintenance, there were further opportunities to detect a problem in the daily inspections and other inspections conducted by pilots. There are dozens of fastenings to inspect when preparing an aircraft for flight, and it is comparatively rare to find a problem. The high number of fastenings and low expectancy of a fault can predispose people inspecting aircraft to miss items. As all inspections carried out by pilots following the release of the aircraft to service were visual, they would not have detected the fault unless they sighted clearly broken torque seal on the relevant union.
In summary, an independent inspection following installation of the power turbine governor was probably not conducted, and document verification processes did not detect that the independent inspection had not been recorded. As a result, the helicopter departed for low-level operations without assurance of continued airworthiness. The exact reasons why these errors occurred could not be determined. However, errors of omission such as omitting the independent inspection, and not completing the associated documentation, can be associated with distractions, and the investigation noted that distractions were potentially associated with work in the hangar at the time,
Preparation of aircraft and crew operating at low-level
Introduction
To conduct the shooting task, the helicopter was periodically required to operate at a height of about 50 ft over a lightly wooded area. Accordingly, the configuration of the cabin and crew at any point in such a low-level operation is likely to be the configuration for impact with terrain should anything occur. Consideration must therefore be given to:
cabin suitability
personal protective equipment (PPE)
restraints
brace positions
other emergency procedures
awareness of risk.
Cabin suitability
The spotter’s injuries were worsened by the radio installation in the front passenger footwell. Although adopting a brace position, with feet flat on the floor would have helped reduce the injury risk, it is very likely that the spotter would have had a lower level of injury without the radio installation in that location.
It should also be noted that the crashworthiness of small helicopters and aeroplanes has improved over the years with changes in certification and manufacturing requirements. This includes improvements in requirements related to impact forces, injurious objects, restraints, fuel tanks and other aspects to reduce the risk of fire. Organisations who have personnel involved in low-level operations can consider these aspects when deciding what types of helicopters should be used for their activities.
Personal protective equipment
Personal protective equipment (PPE) should be used as the last resort to minimise injury risk, but for some aviation operations it is not possible to reduce the risk to an acceptable level without also including PPE. Low-level flight is one of those aviation operations.
Only the pilot wore a helmet, which they provided themselves. Although the pilot was unconscious following collision with terrain, they had no further head injuries.
Although helmets were required by the Director of National Parks’ (DNP’s) safe operating procedures (SOPs) for aerial culling crews, they were not supplied to the crews, and not worn on a routine basis. It is very likely that the shooter’s level of head injury would have been reduced if they were wearing a helmet.
Restraints
The seatbelts with upper torso restraints (UTRs) worn by the pilot and the spotter likely played a role in minimising the severity of upper body and head injuries.
Unfortunately, for some helicopters, such as the B206B3 JetRanger, use of a fall-arrest harness for the shooter was necessary to conduct the shooting task and a seatbelt could not be worn at the same time. However, in the event of a forced landing when in low-level flight, the shooter has no time to transfer to the seatbelt. This exposed the shooter to a higher level of risk due to the increased flail envelope. In this case, possibly due to the movement afforded by the harness, the shooter received a serious injury to their head and right hip.
Brace positions
The helicopter operator provided detailed information about brace positions for seats fitted with UTRs and seats fitted with just lap belts. In this case, probably associated with the limited time available and the surprise of the unfolding events, the spotter did not keep their feet firmly on the floor. This increased their risk of injury, particularly to their lower legs. More specifically, if they had adopted the specified brace position, it is likely the severity of their leg injury (contacting the radio installation) would have been reduced.
Under the Civil Aviation Safety Authority (CASA) instrument for using a fall-arrest harness, the helicopter operator (via the pilot) was required to provide a briefing on the procedures to be adopted to afford the best protection to crewmembers in the event of a forced landing. In this case, the aerial culling crews reported that they were not provided with any such briefing information. While briefings regularly took place, a brace position specific to a harness was not communicated.
It is acknowledged that there is very little information available, provided by CASA or other regulators, about suitable brace positions for a person wearing only a harness. Nevertheless, there is still a requirement on the operator to research and provide information on a suitable position. The extent to which a suitable brace position would have been able to reduce in jury risk in this case could not be determined.
Emergency procedures training for low-level flight
Renewal of the CASA-issued approvals for discharging firearms from an aircraft only required that the applicant had to complete an initial aerial-platform shooting course, and then have shot from an aircraft within the last 2 years.
The shooter and the spotter (who was also a shooter) had not conducted a full or refresher aerial platform shooting course, which included safe practices around helicopters, in almost 20 years. Although they had received pre-flight safety briefings numerous times, such briefings do not cover some of the essential procedures necessary to minimise risk in the aerial shooting task. Had the spotter and the shooter regularly trained and practiced in helicopter safety and emergency procedures, it is likely that they would have both been better prepared for the forced landing.
In particular, the shooter knew the rifle should be thrown from the helicopter yet had not practiced for such an event. There was very little time for the shooter to think about throwing the rifle clear of the helicopter, and the rifle remained in the cabin. Although the barrel was pointed down, the live firearm being in the helicopter increased the potential consequences of the accident. If the action of throwing the weapon in response to an emergency had been rehearsed or drilled, it would have been more likely to be ejected from the aircraft.
Awareness of risk
The CASA instrument also required the helicopter operator to advise personnel using a harness of the ‘inherent limitations and potential risks involved in the use of such a harness’. Aerial culling personnel using the harnesses reported that they were not made aware of the risks associated with harness use, nor precautions to be taken such as brace positions.
The high time aerial culling crew involved in this accident had a good understanding of the risks of the operation and revision of the risks from the operator would probably not have altered their intent to participate. However, another crew may not have been so experienced.
Harness instrument
The language of the CASA instrument regarding use of safety harnesses appeared to allow the use of a harness in lieu of seatbelts for take-off and landing. Equipment approved under CASA regulations (such as anchor points and harnesses) can be reasonably understood to meet the conditions of the instrument. However, CASA advised that the manufacturers’ caveats on use of these items of equipment meant that a seatbelt still had to be worn for take-off and landing.
CASA advised that the instrument was never intended to allow safety harnesses to be worn in lieu of seatbelts during take-off and landing, and that the conditions of the instrument prevented this from occurring. There appeared to be two specific meanings of the word ‘approved’ which could cloud interpretation of the instrument; one in the sense of the equipment being approved under Civil Aviation Safety Regulation 21, and the other of the equipment manufacturers approving their products for certain activities. The equipment requirements of the instrument did not make this distinction clear.
Both the language of the instrument and conflicting use of ‘approved’ opened the instrument to misinterpretation. The language and conditions of the instrument should be improved. Operators and pilots should be aware that, even though an instrument may appear to permit an activity, the limitations of the equipment used must be observed.
Risk management of aerial culling activities
Significant changes had been made to the Director of National Parks’ aerial culling operations in the KNP in the near 4-year period between the risk management plan development in 2015, and the undertaking of the aerial culling program in May 2019. This included, in 2016, the DNP designing the aerial culling task for three crew, introducing a spotter.
Given the increased complexity and risk in low-level operations, the number of crew should be kept to a minimum. That is, only personnel essential for conducting the task should be carried. In this case, the spotter was added to the crew without any formal or systematic consideration of the increased safety risk.
When pursuing a course of action, if one particular stakeholder risk presents the greatest threat, decision makers are prone to adopt a risky strategy which directly addresses the immediate threat to the detriment of other stakeholders (Jawahar and McLaughlin 2001). The spotter had been built into the program, primarily to collect data for stakeholders. Requiring a spotter to be on board mitigated a corporate stakeholder engagement risk, yet exposed the spotter to a high-risk aviation activity. Expanding the crew beyond the industry proven two crew model should have been a trigger for a formal risk analysis and assessment of controls.
A method of data collection designed for two crew or data collection managed through communication with ground crew would have exposed less people to risk. However, no alternative methods of data collection were explored, and the quality of data between two and three crew operations was not assessed. Therefore, the DNP did not know if lower risk options for data collection were available, or know if the added value to the operation warranted the increased risk exposure.
Additionally, there was no documentary evidence of consideration of the impact of changes in helicopter or operator on the operation. The 2015 aerial culling task risk analysis indicated limited consideration of aviation safety risk, and it is likely that the implications of further changes to the operation were not well understood.
When designing aviation operations, organisations without aviation expertise should seek outside information and expertise. Although the DNP contracted an aviation auditor, their scope of work was to audit against the deed of standing offer. Likewise, the helicopter operator was contracted to deliver services as required by the DNP. Both organisations could have provided valuable input into risk analysis and task design, and neither was called upon to do so.
Furthermore, there was no evidence of a working process to build lessons learned into the aerial culling program. The SOPs did not require task debriefs, and hazard management was not conducted. For example, the aerial culling crew and park management knew that the radio network was unsuitable for the aerial culling task, and that they were unable to remedy it. Being such an important risk control, another solution should have been documented and implemented as an alternative.
Other controls were also not managed or reviewed for effectiveness. Specifically, incorrect emergency contact details on KNP documentation used to authorise the task, expired equipment remaining available for use, and PPE being unavailable to the crew.
High turnover in the role of park manager, and the aerial-culling crew not having a line manager, were reported as reasons for there being no supervision or active management of risk. This limited level of risk management restricted the DNP’s ability to eliminate or minimise risk to the crew, meaning safety risk was not managed, nor was safety assured at an organisational level.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety).
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the engine power loss and collision with terrain of VH-FHW on 21 May 2019.
Contributing factors
A loose union on an engine reference air line unscrewed, creating a leak. The leak caused loss of engine power in flight, resulting in a forced landing.
During installation of the power turbine governor, 4 days prior to the accident, an adjacent downstream attachment of the engine reference air line union was loose and not checked for tightness.
Potentially associated with distractions in the hangar at the time, an independent inspection following installation of the power turbine governor was probably not conducted, and document verification processes did not detect that the independent inspection had not been recorded. As a result, the helicopter departed for low-level operations without assurance of continued airworthiness.
Although compliant with regulatory requirements applying to the helicopter being used, bulky, non-task related equipment was installed in the front left passenger footwell, which increased the level of injury to the spotter during the collision with terrain.
Although the Director of National Parks’ safe operating procedures required shooters and spotters to wear helmets during aerial culling tasks, helmets were not provided or used on a routine basis. (Safety issue)
Associated with the limited time to prepare for the forced landing, the spotter did not adopt the brace position, with feet on the floor, increasing the level of injury to their lower legs.
The Director of National Parks did not actively manage the risk of the aerial culling task being conducted in the Kakadu National Park, or effectively supervise the operation. As a result, an increase in the number of crew, a change in helicopter type and change of helicopter operator all progressed without requisite risk management. This exposed crew to avoidable harm during low-level aerial shooting operations. (Safety issue)
Other factors that increased risk
Associated with the limited time to prepare for the forced landing, the shooter did not eject the rifle in readiness for a forced landing. As such, the cabin was not prepared for a forced landing.
Recurrency training and drills in aircraft emergencies were not required for reissue of an aerial platform shooting permission. Some shooters last conducted training about 20 years prior, during initial issue of their permissions. (Safety issue)
Although required by the harness instrument commonly issued by the Civil Aviation Safety Authority, the operator did not appraise shooting crews of the risks of using only a harness for restraint during low-level flight. (Safety issue)
A harness instrument, commonly issued by the Civil Aviation Safety Authority (CASA), stated that a harness could be used instead of a seatbelt for take-off and landing. Although not intended by CASA, this instrument was easily able to be misinterpreted as indicating that a seatbelt was not required to be used during take-off and landing. (Safety issue)
Other findings
To conduct the shooting task, the helicopter was periodically required to operate at a height of around 50 ft over a lightly wooded area. This reduced opportunity to prepare for and make a successful forced landing.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: Although the Director of National Parks’ safe operating procedures required shooters and spotters to wear helmets during aerial culling tasks, helmets were not provided or used on a routine basis.
Safety issue description: The Director of National Parks did not actively manage the risk of the aerial culling task being conducted in the Kakadu National Park, or effectively supervise the operation. As a result, an increase in the number of crew, a change in helicopter type and change of helicopter operator all progressed without requisite risk management. This exposed crew to avoidable harm during low-level aerial shooting operations.
Safety issue description: Recurrency training and drills in aircraft emergencies were not required for reissue of an aerial platform shooting permission. Some shooters last conducted training about 20 years prior, during initial issue of their permissions.
Safety issue description:A harness instrument, commonly issued by the Civil Aviation Safety Authority (CASA), stated that a harness could be used instead of a seatbelt for take-off and landing. Although not intended by CASA, this instrument was easily able to be misinterpreted as indicating that a seatbelt was not required to be used during take-off and landing.
Safety issue description: Although required by the harness instrument commonly issued by the Civil Aviation Safety Authority, the operator did not appraise shooting crews of the risks of using only a harness for restraint during low-level flight.
Safety action not associated with an identified safety issue
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Additional safety action by Jayrow Helicopters
Following inspection of VH-FHW on site, the helicopter operator:
immediately actioned a fleet wide check and retorque of engine flexible and rigid oil, air and fuel lines/hoses/pipes attachments
improved procedures for use of third party harnesses aboard company aircraft
outsourced human factors training for engineers which expanded quality and content of the training.
Additional safety action by Director of National Parks
Following the accident, the Director of National Parks immediately suspended aerial culling activity.
In January 2021, the DNP advised of the following safety actions:
upgraded handheld radios with higher wattage, providing improved communications channels through broader broadcast range for staff undertaking aviation activities. The use of these radios is prioritised for staff undertaking remote work…
As part of their broader commitment to ensuring safety in aviation activities, the DNP and department have also established a program of work relating to aviation activity risk management and mitigation. This includes:
establishing an updated enterprise WHS Information System (WHSIS), with the planned implementation of incident reporting and hazard modules to occur in early 2021. The WHSIS will assist with recording and managing risks and hazards in relation to high-risk operational activities including aviation activity risks
infrastructure investment in the KNP radio and telecommunications network. For example, a total of $7 million has been committed to a new tower network within KNP and planning for those infrastructure upgrades is underway; and procurement of additional handheld radios and personal tracking/emergency call devices for staff working on the park
establishment of a Departmental Focus Group, being a group comprised of operational staff/business areas undertaking aviation activities (including aerial culling operations) and WHS/risk and business continuity specialists to take a collaborative approach to addressing WHS critical risks and controls across the portfolio. The group is planned to commence operating in February 2021.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot of the accident flight
pilots and Head of Flight Operations of the aircraft operator
engineers of the approved maintenance organisation
aerial culling crew on board the helicopter and other Parks Australia personnel
Civil Aviation Safety Authority
engine manufacturer
crew restraint harness manufacturer
aerial platform shooting subject matter experts
Northern Territory Police
recorded data from the GPS unit on the aircraft.
References
Civil Aviation Safety Authority 2013, Safety Behaviours: Human Factors Resource Guide for Engineers, Canberra, ACT.
Hart T & Sander A 2016, Memory and Moderate to Severe Traumatic Brain Injury, Model Systems Knowledge Translation Center, VA, USA.
Hobbs A, 2008, An Overview of Human Factors in Aviation Maintenance, Australian Transport Safety Bureau, Canberra, ACT
Jawahar M & McLaughlin GL 2001, Toward a descriptive stakeholder theory: An organizational life cycle approach, Academy of Management Review, 26(3): 397–414.
Motley EB 2006, Aircraft Accident Survivability: Rotary Wing Aircraft, Naval Air Warfare Center, MD, USA.
Nadine B. Sarter & Heather M. Alexander (2000) Error Types and Related Error Detection Mechanisms in the Aviation Domain: An Analysis of Aviation Safety Reporting System Incident Reports, The International Journal of Aviation Psychology, 10:2, 189-206, DOI: 10.1207/S15327108IJAP1002_5
North Atlantic Treaty Organization 1989, The Human Factors Relating to Escape and Survival from Helicopters Ditching in Water, AGARD-AG-305E, Canada.
Reason J & Hobbs A, 2003, Managing Maintenance Error: A practical guide, CRC Press, Boca Raton, USA.
Transport Canada 2016, Advisory circular: Brace for Impact Positions for all Aircraft Occupants, AC 700-036, Ottawa, Canada.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
pilot of the accident aircraft
aerial culling crew on board the helicopter
helicopter operator
approved maintenance organisation
engine manufacturer
Director of National Parks
Civil Aviation Safety Authority.
Submissions were received from the:
helicopter operator
Director of National Parks
Civil Aviation Safety Authority.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
The ATSB has assisted the Myanmar Accident Investigation Bureau’s investigation of a collision with terrain involving Biman Bangladesh Airlines – DHC-8-402Q, registered S2-AGQ, Yangon-Mingaladon Airport, Myanmar on 8 May 2019.
The aircraft was operating on a flight from Shahjalal International Airport, Bangladesh to Mingaladon Airport, Myanmar. On board were six crew and 28 passengers. Weather at Yangon was reported as poor, due to the presence of a thunderstorm in the area. The aircraft collided with Runway 21 at Yangon-Mingaladon Airport, Myanmar during the landing phase. The aircraft was destroyed and twenty occupants were reportedly injured.
The aircraft cockpit voice recorder (CVR) and flight data recorder (FDR) from S2-AGQ were brought to Australia by two senior Myanmar investigators on 10 June 2019. In the presence of the Myanmar investigators, both recorders were successfully downloaded on the 11 and 12 June 2019 at the ATSB data recovery facility in Canberra, Australian Capital Territory. In addition, the ATSB assisted the Myanmar investigation team with preliminary factual analysis of the recorded data. All data recovered from the CVR and FDR was provided to the Myanmar investigators to assist with their Annex 13 investigation.
The ATSB also assisted the Bangladesh Accredited Representative on 27 June 2019 with a replay of the CVR and review of the FDR data.
There are no ongoing actions for the ATSB at this stage. Any enquiries regarding the investigation should be addressed to the Myanmar Accident Investigation Bureau at the contact details listed below:
Myanmar Accident Investigation Bureau First Floor, DCA HQ Building (B) Yangon 11021, Myanmar Tel: 951 533162 Fax: 951 533016 Email: aungmaw23@gmail.com
On 14 April 2019, an Aeroprakt A22LS Foxbat collided with terrain while conducting mustering operations on Aldville Station approximately 120 km north-west of Cunnamulla, Queensland. The aircraft sustained substantial damage and the pilot was fatally injured.
Recreational Aviation Australia (RAAus) is investigating the accident and has requested assistance from the Australian Transport Safety Bureau (ATSB) in:
recovering data from an on-board GPS unit
conducting metallurgical and failure analysis on components of the aircrafts control system
conducting failure analysis on the aircraft’s damaged wing covering.
To facilitate this work the ATSB has initiated an external investigation under the Transport Safety Investigation Act 2003.
Any enquiries relating to the accident investigation should be directed to RAAus at: www.raa.asn.au.
Final Report
What happened
On 14 April 2019 an Aeroprakt A22LS Foxbat, registered 24-8140, collided with terrain while conducting mustering operations on Aldville Station, approximately 120 km north-west of Cunnamulla, Queensland. The pilot was fatally injured and the aircraft sustained substantial damage.
Recreational Aviation Australia (RAAus) commenced an investigation and requested assistance from the ATSB to:
conduct detailed examination of a control system component and a section of wing fabric
download data from a damaged GPS unit that was on board the aircraft at the time of the accident.
To facilitate this work, the ATSB initiated an external investigation under the Transport Safety Investigation Act 2003.
Results
The ATSB conducted visual inspections and microscopic analyses on an eyebolt from the control system (Figure 1) and a piece of damaged wing fabric. Analyses of the eyebolt determined that it had failed due to overstress with no indication of fatigue. The wing fabric analyses indicated that the damage was consistent with that expected as a result of the ground impact.
Figure 1: Failed eyebolt showing fracture surface
Source: ATSB
The ATSB undertook data recovery from an accident damaged Lowrance Airmap 2000c GPS unit. A raw binary data file was recovered through a direct download of non-volatile memory. The file was unable to be interpreted by the ATSB and was supplied to RAAus.
With the completion of the examinations and data recovery, the ATSB has concluded its involvement in the investigation of this accident. Any further enquiries in relation to the investigation should be directed to Recreational Aviation Australia.
___________ This report has been released in accordance with section 25 of the Transport Safety Investigation Act 2003.
On 20 March 2019, the pilot of an Airbus Helicopters AS350B3e, registered VH-SZS (SZS) was performing aerial work on Pernatty Station, South Australia, approximately 60 km east of Woomera Airfield. The task involved helicopter powerline stringing from the Mount Gunson South substation to the Carrapateena mine site, a total distance of 51 km. The stage being conducted on the morning of 20 March was from pole 159 to pole 179, a distance of 4.8 km. Stringing operations continued normally for poles 161, 162 and 163. However, while approaching pole 164, at about 1017, witnesses reported seeing the helicopter collide with the pole and impact terrain near the base of the pole. The pilot, who was the sole occupant, received fatal injuries.
What the ATSB found
The ATSB found that shortly after the pilot was trained in powerline stringing, for unknown reasons they modified the taught stringing methodology. The new methodology placed the helicopter at low level in the vicinity of the powerline poles, increasing the risk of a collision. It also exacerbated the uptake of dust which, in combination with the position of the sun and the rearward attitude of the aircraft likely reduced the pilots’ visibility of pole 164 and their situational awareness of it.
These factors, combined with the short distance and large elevation gain between pole 163 and 164, led to the pilot inadvertently colliding with pole 164. It was also found that the indirect supervision provided to the newly trained pilot was ineffective in identifying that a modified stringing method was being used.
What has been done as a result
The helicopter operator has advised the ATSB that they have made the following changes to their operations manual. The changes relate specifically to the supervision and review of newly authorised pilots in specialist tasks, and includes:
Mandated and expanded In Command Under Supervision time requirements for pilots as part of initial task training for relevant specialist tasks.
The introduction of consolidation flight checks at key points for pilots newly authorised in relevant specialist tasks.
The mandated extension of time that pilots newly authorised in relevant specialist
tasks are mentored by an experienced pilot.
Safety message
This investigation shows that experience alone will not always prevent a pilot from having an accident. In this case the pilot was a very experienced deputy chief pilot with nearly 6,500 flight hours. The ATSB research publication AR-2012-035 provides some insight as to why experience does not always provide a safeguard:
Experience alone can never compensate for high risk activity.
Sound decision-making and experience do not necessarily go together.
Using pilot experience as mitigation for potential operational risks is inadvisable. If the risks are unacceptable for a qualified and competent pilot, there should be no reason for an experienced pilot to accept them.
The investigation also highlights the value of direct supervision of pilots who have recently been trained in a new task.
The occurrence
On 20 March 2019, the pilot of an Airbus Helicopters AS350B3e, registered VH-SZS (SZS) was performing aerial work on Pernatty Station, South Australia, approximately 60 km east of Woomera Airfield (Figure 1).
Figure 1: Accident location
Source: Google Earth, annotated by ATSB.
The helicopter operator (Aeropower) had been contracted to conduct powerline stringing operations (see the section titled Power line stringing methodology) for a new 132 kV electrical transmission line from the Mount Gunson South substation to the Carrapateena mine site (operated by OZ Minerals). The task involved stringing draw wire[1] and optical ground wire. The total length of the stringing operations, 51 km, was divided into twelve stages that were identified with reference to numbered transmission poles. The stage being conducted on the morning of 20 March was from pole 159 to pole 179, a distance of 4.8 km.
On the morning of the accident the Aeropower pilot and refueller rose at about 0430 Central Daylight‑saving Time.[2] After breakfast, at about 0630 they attended the first of three morning briefings. The first briefing was run by Ventia, the primary contractor for the powerline operation (see the section titled Operational information). All workers were breath-tested for alcohol during this briefing. After the Ventia briefing, the Aeropower duo then attended the Powerlines Plus (PLP) briefing at about 0700. After the PLP briefing, at about 0730, the refueller drove the pilot to the nearby Carrapateena Airport.
At 0842 the pilot took-off from Carrapateena Airport. After about two minutes of flight, the pilot returned the aircraft to the airport due to what was later described as a warning light in the cockpit. After about seven minutes on the ground, the pilot took-off again and flew to pole 179 (the last pole of the stage) for a radio check with the stringing team ground-crew. The pilot then flew the length of the stage to the start point (pole 159) for a fly-by inspection of the job site. The pilot then flew to the refuelling point, nick-named the ‘Turkey’s nest’, landing at about 0858 (Figure 2). Here the pilot rendezvoused with the refueler and the stringing team for the last pre-start briefing for those workers directly involved with the helicopter operations.
During this meeting the pilot briefed one of the ground crew, supplied by the powerline company, on how to hook-up the draw wire to the helicopter as they had not performed this task previously. The aircraft was also refuelled. Afterward, the stringing team proceeded to their assigned work positions and at about 1000 the pilot took off and proceeded to pole 159 to commence stringing operations.
Figure 2: ADS-B[3] derived flight data for VH-SZS on 20 March 2019.
Figure 2 Shows the ADS-B flight data for VH-SZS on the day of the accident.
Source: FlightRadar24 and Google Earth, annotated by ATSB.
In preparation for helicopter stringing operations, the draw wire had previously been strung to a pulley on pole 159 using an elevated work platform. Just after 1000, when SZS reached pole 159, ground crew attached the draw wire to a remote hook fitted to the helicopter at the end of a 30 ft longline. SZS then pulled the draw wire out from a Tesmec S.p.A.[4] (Tesmec) stringing machine and proceeded to pole 160 to clip the draw wire into the pulley. Stringing operations continued normally for poles 161, 162 and 163.
While approaching pole 164 at about 1017, witnesses reported seeing the helicopter collide with the pole and impact terrain near the base of the pole. Several ground crew from the stringing team that were near the helicopter came to assist. They extinguished a small post-impact fire and removed the pilot from the aircraft to a safe distance. A short time later emergency services and paramedics from the mine site attended the scene and confirmed that the pilot, who was the sole occupant, had received fatal injuries.
The pilot held commercial pilot licences for both aeroplanes and helicopters, issued on 17 November 2000 and 20 November 2009 respectively. The pilot was rated for both single‑ and multi-engine fixed wing aircraft, as well as single‑engine helicopters. Design feature endorsements that the pilot held included manual propeller pitch control, tail wheel, gas turbine and retractable undercarriage endorsements. Additionally, the pilot had a low-level endorsement for helicopter sling operations issued on 17 November 2009 and an aeroplane aerobatic endorsement, issued on 8 January 1998. The pilot was also a licenced aircraft maintenance engineer.
A review of the pilot’s Air Maestro[5] logbook showed that at the time of the accident the pilot had accumulated a total flying experience of approximately 6,370 hours. About 45 of those hours were in the previous 30 days and about 77 hours were in the last 3 months. Most the pilot’s flying experience (5,280 hours) was in helicopters, and the majority of that (4,537 hours) was in the MD500, a single‑engine light utility helicopter. The pilot had 240 hours on the AS350, the same type flown on the day of the accident, with about 49 hours in the last 3 months on that type. The pilot’s licence book indicated that the pilot had last completed a single-engine helicopter flight review on 24 Jan 2019 that was valid for 12 months.
Powerline stringing training
The pilot, who was the deputy chief pilot (DCP) for Aeropower Pty. Ltd., had been with the company since the late 1990s. In that time, the pilot had accrued about 2,400 hours in powerline operations. This included about 1,343 hours in powerline patrol and inspection, 643 hours insulator washing and nearly 400 hours in platform work.
The DCP had observed powerline stringing operations in December 2018, on a job in Wollongong, New South Wales. However, all the DCPs formal powerline stringing training was conducted during the three days of the first tour at Carrapateena.
The training involved the:
DCP observing the chief pilot (CP) from the ground
DCP observing in the aircraft
CP observing the DCP while flying dual
DCP stringing solo with the CP observing from the ground.
The DCP was deemed satisfactory in all requirements and on 7 February 2019 the CP signed-off the DCP for powerline stringing operations. The training comprised a total 7.2 hours with 1.4 hours of those with the DCP in command. At the time of the accident the pilot had a total of 25 hours experience in powerline stringing.
Medical information
The pilot held a Class 1 Aviation Medical Certificate that was valid until 2 Oct 2019 with no restrictions. The pilot was reported to be very fit and active and displayed normal behaviour on the morning of the flight and was well-rested. He was not reported to be taking any prescription medications and had no reported medical condition that could have affected his ability to operate an aircraft that day.
A post-mortem examination identified no significant background natural disease, which could have contributed to the accident. Toxicological analysis concluded that the toxicology was also non‑contributory to either the accident or cause of death.
Aircraft information
Overview
VH-SZS (SZS) (Figure 3) was an Airbus Helicopters[6] AS350B3e Écureuil (Squirrel) light utility helicopter manufactured in 2012. The aircraft was a single-engine helicopter with six seats in the basic configuration. The primary structure of the aircraft was constructed of sheet metal, while the canopy, underside access cowling, transmission and engine cowlings were made of composite materials. The cabin area was accessible through four doors, two hinged pilot doors and two sliding rear doors.
Figure 3: Image showing VH-SZS
Figure 3 shows VH-SZS, a single turboshaft‑powered Airbus Helicopters AS350B3e Squirrel.
Source: Supplied
Engine and rotors
The main rotor system comprised of three composite main rotor blades constructed of a fiberglass spar with a composite skin over a foam core. The blades were attached to a composite semi-rigid, bearingless starflex hub. The two-blade tail rotor was also manufactured of composite materials moulded onto a fibreglass spar. The tail rotor was mounted to a lightweight sheet metal tail boom. All flight controls were hydraulically boosted, with hydraulic power supplied by a single hydraulic pump which was belt driven by the engine-to-transmission driveshaft. SZS was powered by a Turbomeca Arriel 2D engine, which was a free turbine[7] turboshaft engine. The engine was controlled by a dual-channel, full authority digital engine control (FADEC) system.
Engine Data recorder
The aircraft was fitted with a Sensorex Engine Data Recorder (EDR). The EDR was a light recorder that exclusively records data sent by the FADEC system for maintenance purposes. For both FADEC channels, engine parameters and failure flags were recorded. Engine parameters were recorded continuously at a sample rate of 1 second and at a sample rate of 20 ms for a limited duration when a failure occurs.
Maintenance
The helicopter was built in 2012 and operated in New Zealand before being imported to Australia in 2016. A Certificate of Airworthiness inspection was completed 11 March 2016, and the certificate of registration was transferred to the current owner on 13 December 2018. SZS had a current maintenance release, issued on 19 October 2018 which was valid for a period of 150 hours or 12 months, whichever was sooner. At the time of the accident the aircraft had accrued 100.4 hours since the maintenance release. The maintenance release was not in the helicopter, as required, it was located in the pilot’s belongings in the accommodation area.
The helicopter was maintained in accordance with the manufacturer’s documentation. At the time of the accident, there were no known maintenance deficiencies with the helicopter.
Aircraft weight and Balance
A weight and balance was performed on 16 January 2019 with an expiry date of 15 January 2022. Additionally, weight and balance calculations indicated that the aircraft was below maximum take‑off weight and within the centre of gravity limits for the duration of the flight
Mack Pull
To facilitate stringing operations, the helicopter was fitted with a Mack Innovations (Australia) Pty Ltd (Mack Pull) bidirectional line stringing system. The Mack Pull provides a hard point located under the belly and to the side of the aircraft that is designed to carry a standard cargo hook. It assists with aerial work applications that require sideways flight and was specifically designed for power cable stringing work as it helps to keep the cable within the pilots’ field of vision.
A 30 ft longline was attached to the cargo hook on the Mack Pull and a Mechanical Specialties 301 remote hook was attached to the other end of the 30 ft longline. A cockpit mounted load meter gave a visual indication to the pilot of the load placed on the system. The load rating on both the remote hook and the 30 ft longline was 3,000 lbs (1,360 kg).
Flight recorders
The aircraft was not fitted with a flight data recorder or a cockpit voice recorder, nor was either required by regulations.
Meteorological information
Graphical Area Forecasts (GAF)[8] for the area of operations, as well as aerodrome forecasts (TAF), meteorological aerodrome report (METAR)[9] and Automatic Weather Station (AWS) reports from Woomera Airfield were obtained from the Bureau of Meteorology. The forecasts (GAF and TAF) predicted no significant weather in the area of operations for the duration of the accident flight.
The METARs for Woomera Airfield (about 60 km west of the accident site) at 0930 indicated that the surface wind was 160° (True) at 9 kt. At 1000 the wind was 170° at 10 kt and at 1030 the wind was 160° at 9 kt. For all times the QNH[10] was 1015 hPa and the conditions were CAVOK.[11]
At the time of the accident the Woomera AWS recorded the temperature at 24.4 °C, 8 knots of wind (with maximum gusts of 10 kt) from 166°, and a QNH of 1015.8.
Weather data measured at the Carrapateena mine showed that at 1010 (about 7 minutes before the accident) the temperature was 27.5 °C and the wind was 1.7 kt from 128°. There were no significant changes in those conditions on the morning leading up to the accident.
On-site observations
Observations of the conditions on the day were consistent with the meteorological reports. It was reported that during the last pre-flight briefing the pilot commented that the conditions were good for flying. Other witnesses described the conditions as sunny and a little bit windy. Several witnesses noted both the strength and position of the sun, which was reported to be in the direction that the aircraft was travelling. Geoscience Australia data showed that at the time of the accident the azimuth[12] of the sun was 65° and its altitude was 35°. The bearing from pole 163 to pole 164 was 49°.
Additionally, the presence of a large amount of dust in the vicinity of the aircraft was noted by several witnesses. This can be seen in Figure 4, which shows a sequence of images of the aircraft traversing from pole 163 to pole 164.
Figure 4: VH-SZS traversing between pole 163 and 164.
Figure 4 shows VH-SZS traversing between pole 163 and 164. Pole 163 is visible in the image, while pole 164 is out of the frame to the right. The direction of travel is from left to right in this image.
Source: Witness
Wreckage and accident site information
Accident site
The accident site was located about 60 km east of Woomera South Australia, on the OZ Minerals Carrapateena mine site (Figure 1). The mine is located on Pernatty Station, a 2,147 km2 livestock station about 136 km north of Port Augusta. The start of the stringing stage (pole 159) was about 5 km south-west of Carrapateena Airport and the aircraft had traversed about 1 km to pole 164.
Wreckage examination
Site and wreckage examination did not identify any aircraft defects or anomalies that might have contributed to the accident. Markings on pole 164 (Figure 5) indicated that the helicopter collided with the pole about 17 m above the ground. The main rotor blade (MRB) contacted the pulley mounted on the insulator, the ladder and pole during the accident sequence. The pulley fractured from its mounting bracket and came to rest on the access road, 15 m from the pole. The ladder was struck and bent toward the direction of the pulley, consistent with the direction of rotation of the MRBs. The pole had a number of MRB strikes, which progressed in a downward direction as the helicopter descended (inset in Figure 5).
Figure 5: Impact marks and damage to pole 164.
Source: ATSB
After impacting the pole, the helicopter came to rest on its right side approximately 2 m from the base of the pole (Figure 6). The aircraft had rotated approximately 90° to the left of its direction of travel.
Figure 6: The accident site near pole 164. The direction of travel of the helicopter was from pole 163 to pole 164.
Source: ATSB
The cockpit and fuselage roof were substantially disrupted from impact forces. The tail boom had almost entirely detached at the fuselage junction and fractured forward of the horizontal stabiliser, due to ground impact. Two of the MRBs had separated from the rotor head and came to rest side‑by‑side next to the fuselage. The third blade remained attached and had become entangled around the main rotor gearbox.
The longline, which had separated from the Mack Pull, was found a short distance away toward Pole 163. The draw wire was also found to have separated from the remote hook on the longline. The ATSB recovered a number of components from the accident site for further examination.
Engine
The engine assembly was examined and found to be complete with no evidence of pre-accident defects. All engine plumbing and wiring looms were connected to their respective components. The chip detector and magnetic plugs were examined and found to be clear of particles. The engine fuel and oil filters were examined and found to be clear of contaminants.
Recorded engine data
The engine data recorder (EDR) was shipped to France and downloaded by the of Bureau d’Enquêtes et d’Analyses (BEA). The BEA analysed the data in consultation with the aircraft manufacturer (Airbus Helicopters) and the engine manufacturer (Safran Helicopters Engines). The analysis showed that the engine was performing in a satisfactory manner until contact with the pole, when the EDR recorded a torque overlimit. The BEA report concluded that;
No anomaly was found prior the impact with the ground/pylon.
Fuel
SZS was fully fuelled on the morning of the flight from an intermediate bulk container (IBC), which was owned and maintained by the operator. The amount of Jet A1 taken aboard was 315 litres, which was sufficient to carry out the planned work for that morning.
A fuel sample was taken from the aircraft post-accident and from the IBC. Both series of testing indicated that the fuel was clean and clear of any contaminants.
Instruments and Avionics
The instrument panel fitted to SZS was the basic panel with added turn and slip and glideslope indicators. An air conditioning control panel and hour meter was also installed.
Emergency Locator Transmitter (ELT)
SZS was fitted with a KANNARD 406 AF-H ELT. The ELT, with part number S1822502-02 and serial number LX1100019317, had an expiry date of November 2024. The ELT activated automatically during the accident sequence and was deactivated by an attending police officer.
Flight controls
All flight controls were examined, and control continuity was established for both main and tail rotor systems. A number of control tubes displayed bending damage due to contacting the surrounding structure during the accident sequence.
Mack Pull and longline
An examination of the Mack Pull and cargo hook did not reveal any defects. Company standard practice was to install the longline with a shackle at both ends however, the draw wire did not have a shackle fitted for the connection to the remote hook. The upper end connected to the helicopter hook did have the shackle installed as required.
The remote hook and longline detached from the aircraft cargo hook during the accident and were located a short distance from SZS, drawn backwards by the retracting load of the draw wire. It could not be determined how it unhooked from the Mack Pull cargo hook. After detaching from the Mack Pull, the remote hook struck a large rock, indicated by orange paint transfer from the hooks’ outer cage. The hook then bounced to another location, shown by a ground scar. The draw wire was found detached from the remote hook. On-site testing indicated it was likely the uncoupling of the draw wire occurred during the impact with the rock.
Post impact fire
A small post impact fire occurred at the engine exhaust. Responders used hand-held fire extinguishers to prevent the spread of fire to the airframe. The resulting damage was minimal and did not show evidence of a fire outside of the engine exhaust.
Additional information
Operational information
The pilot, who was the deputy chief pilot (DCP) for Aeropower and the chief pilot (CP) mobilised to Adelaide on 31 January 2019 in preparation for operations at Carrapateena. The intention was that the CP would use this job as an opportunity to train the DCP in powerline stringing operations, then once signed-off, the DCP would complete the rest of the job solo. On 3 February both pilots mobilised to Port August and arrived at Carrapateena on 4 February for an all-stakeholder briefing for the stringing operation. The key stakeholders present were:
OZ Minerals – the mine site operator
Ventia – Principal contractor
ElectraNet – Contracted to build, own, operate and maintain the powerline infrastructure
Powerlines Plus (PLP) – sub-contracted by Ventia to build the powerline
Aeropower – contracted by PLP for the helicopter stringing operations.
Later that day the Aeropower pilots were audited by an independent safety auditor contracted by ElectraNet to assess their capability to safely undertake the job. At this point Aeropower were already contracted to do the work. The next day, 5 February, flying operations began.
Summary of stringing operations
Tour 1 of the helicopter powerline stringing operations started on 5 February and continued until 7 February. During these 3 days, stages 5 and 6 were completed. Stage 5 comprised 22 poles while stage 6 comprised 21 poles. Each stage was completed thrice, once for each of the three wires suspended by the poles. At the end of tour 1, on 7 February, the DCP was signed-off on powerline stringing and the CP departed the site.
Stringing for tour 2 started on 18 February and was conducted by the DCP solo, without the CP on-site. Stage 7 (15 poles), was completed on 18 February and stage 8 was completed on 19 February (19 poles). Again, all stages were conducted three times.
Tour 3 stringing operations commenced on 10 March with the 20 poles of stage 4. This was followed the next day with stage 9 (21 poles). Again, all stages were completed three times by the DCP flying solo. Tour 4 started 9 days later, on 20 March. Including the 4 poles strung on the morning of the accident, the pilot had strung 122 poles, all but the last 4 were strung 3 times.
Accident span gradient
The span width between poles 163 and 164 (the accident span) was 174 m, one of the shortest the pilot had undertaken at Carrapateena. Indeed, of the 122 spans that the pilot had strung at Carrapateena, only 4 were shorter than the accident span. In addition, the elevation gain between pole 163 and 164 was 12.86 m. This was the largest elevation gain of any span the pilot had undertaken at Carrapateena. As a result of the span length and elevation gain, the accident span between pole 163 and 164 had the greatest gradient of any span the pilot had conducted at Carrapateena.
Use of load rings
In response to an ATSB investigation (ATSB report 200300011), the Civil Aviation Safety Authority (CASA) airworthiness bulletin AWB 25-006 was issued (and has since been revised). The bulletin applies to all rotorcraft engaged in underslung load / non-human external cargo. It highlights the importance of using a primary load ring and shackle on cargo hooks to prevent both an inadvertent release or a jammed hook.
The Aeropower operations manual was consistent with this regulatory guidance, with sections 9.1.3 and 9.1.4 stating;
9.1.3. DO NOT put a rope of any kind directly onto the cargo hook. It can twist and hang up preventing release if required.
9.1.4. DO use a shackle or primary load ring to attach directly to the hook to ensure smooth release. Make sure it is large enough to fall free without becoming trapped by the dropping tongue of the hook.
On the day of the accident a Powerlines Plus ground staff was assigned to hook up the draw wire to the helicopter. As they had not performed the task before, during the pre-flight briefing, the pilot instructed the ground staff on the procedure. It was reported that the use of a load ring or shackle was not mentioned, and that the instruction given was to connect the draw wire directly to the remote hook. Other ground staff reported never seeing a load ring or shackle between the draw wire and the remote hook at any time during the Carrapateena operations.
Power line stringing methodology
The purpose of powerline stringing is to attach electrical conductor wire to pulleys that are suspended on towers (or poles). Light-weight conductor wire on smaller poles can be strung using an elevated work platform (‘cherry-picker’) and pulled through with a small winch. While heavier gauge wires, such as that used at Carrapateena, necessitates the use of heavy machinery to pull the conductor between towers. Helicopters can also be used for powerline stringing. The advantage of using helicopters are;
Much faster than pulling a conductor wire with a bulldozer.
Minimised disruption to ecologically or culturally sensitive land (the Carrapateena site had cultural sensitivities).
The ability to traverse rugged terrain that would be inaccessible to ground-based heavy machinery.
One of the limitations of using a helicopter is the weight carrying capacity of the aircraft. For jobs that require a heavy conductor wire, a lighter weight draw wire is strung by the helicopter. Then, a fixed position ground-based winch uses the draw wire to pull the heavier conductor wire back through the pulleys.
Taught methodology
Between 5 and 7 February 2019, the DCP received instruction in helicopter powerline stringing methodology. The stringing method taught by the CP had several key features, these included:
A straight-line flight path is maintained between each pole.
The helicopter hovers and traverses at an angle of about 90° (sideways) to the path of the wire. This ensures that visibility of both poles in maintained. The strung pole should be visible through the right cockpit door/window and the target pole should be visible through either the left cockpit door/window or the open rear left door (Figure 7).
Figure 7: Orientation of helicopter relative to path of travel during stringing operations.
Source: Aeropower work instruction AS350 – Mack Pull
After clipping in the draw wire to the pulley, height is maintained for a short distance to ensure there is enough weight in the line to hold it down on the pulley.
As the helicopter traverses to the next pole, altitude is gained to a height greater than that of the next pole.
The helicopter traverses directly over the top of the target pole. Visibility of the pole is maintained by use of aircraft mounted mirrors.
Once clear on the other side of the pole, the helicopter descends to the height of the target pulley to clip the wire in.
The process continues until the stage is complete.
Observed methodology
The DCP was deemed competent in the stringing method and signed-off by the CP at the end of tour 1 on 7 February 2019. All subsequent stringing operations were conducted by the DCP solo.
Nothing unusual or untoward was observed regarding the stringing methodology during the two days of flight operations of the second tour. However, the Aeropower refueller, who was experienced in stringing operations, never observed the stringing operations due to the location of the refuelling site. During the third tour a different Aeropower refueller was on-site and took photographs and video of the stringing operations. Some of the key points observed were;
After clipping in the draw wire to the pulley the helicopter traversed out to the side (left side relative to direction of travel) en-route to the target pole.
The aircraft did not gain altitude while traversing in-between poles.
The helicopter pulled the draw wire in a pronounced tail-back attitude, with respect to the direction of the pull (Figure 4).
Rather than traversing directly over the target pole, the helicopter came back in from the left side and came over and around the pole.
This modified technique continued into tour 4 and was observed by a number of witnesses on the day of the accident. Witnesses stated that the helicopter never came above the height of pole 164 before colliding with it.
ADS-B data (Figure 8) from the day of the accident shows a flight path consistent with what was described by witnesses. The data shows that the aircraft maintained a low altitude between poles. Only once in close proximity to the next pole did the aircraft rise above the height of the pole. The data also shows the aircraft tracking to the left of the direct path and traversing around the pole rather than directly over it.
Figure 8: ADS-B data of the flight path from pole 159 to 164
Source: FlightRadar24 and Google Earth, annotated by ATSB.
Regulatory oversight
Other than the low level and sling operations endorsements, there are no other specific Civil Aviation Safety Authority (CASA) requirements for undertaking powerline stringing operations. Additionally, there are no recommendations or requirements from CASA regarding the training requirements for operators training pilots in powerline stringing. Nor are there any requirements for any supervision post-training. It is up to the individual operators to provide what they determine to be an appropriate syllabus of training and supervision.
The pilot was provided the training required by Aeropower procedures and satisfied all CASA and Aeropower requirements to conduct powerline stringing. Although there was no requirement in Aeropower procedures for post-training supervision, the CP did try to provide indirect supervision after they had left Carrapateena. The CP stated they were in regular contact with the DCP during tours 2 and 3 to check up on how the DCP was going. It was reported that the DCP did not raise any concerns regarding the job or the stringing methodology.
Related occurrences
A review of the ATSB’s national aviation occurrence database revealed only one other occurrence reported to the ATSB in the 20 years between 2000 and 2019 involving helicopter powerline stringing operations. That accident, also involving an Aeropower aircraft, was investigated by the ATSB (Investigation report AO-2008-025). A summary is below.
On 9 April 2008, the crew of a McDonnell Douglas Helicopter Company MD369ER helicopter registered VH-PLU, experienced a substantial loss of engine power while conducting low-level powerline stringing operations. The helicopter impacted the ground and was seriously damaged. The two occupants were seriously injured.
The investigation determined that the pilot in command was operating the helicopter with a fuel tank quantity that did not guarantee continuous operation of the engine at the flight attitudes experienced during the powerline stringing operation.
As a result of the accident, the operator revised its fuel management procedures for powerline stringing operations.
In the same 20-year period Aeropower was involved in the following five accidents that were investigated by the ATSB (this includes AO-2008-025, previously mentioned):
200505332: Loss of tail rotor authority – 9 km north of Warwick Queensland, VH-SUV
AO-2008-025: (Summarised above) Fuel-related event 16 km south-east of Townsville Airport, Queensland 9 April 2008
AO-2008-078: Wirestrike - McDonnell Douglas 369D, VH-PLJ, 13 km north of Murray Bridge, South Australia, 19 November 2008
AO-2012-082: Collision with terrain - Schweizer 269C-1 helicopter, VH-LTO, Redcliffe Aerodrome, Queensland, 18 June12
AO-2016-078: Fuel exhaustion and collision with terrain involving McDonnell Douglas Corporation 369, VH-PLY, 36 km north‑west of Hawker, South Australia, on 17 July 2016
Of note, the wirestrike fatal accident in 2008 (AO-2008-078) involved a pilot that was recently instructed in a new task (platform work – joint-testing). The accident occurred the day after training had completed on the pilot’s first unsupervised joint-testing job. Although experienced, with 3,744.2 total flight hours, at the time of the accident the pilot had a total of about 27 hours on platform work.
The report stated:
Had the chief pilot been able to supervise the task on the day of the occurrence as planned, it was possible that he may have detected one or more of the earlier mid-span transpositions and alerted the crew to the hazard. That would probably have forewarned the crew to anticipate other mid-span transpositions along the line, and increased the likelihood that they would detect the transposition between towers STR0031 and STR0032.
One of the safety factors identified by the investigation was;
There was no direct supervision of the joint-testing operations [Minor Safety issue].
Bureau of Meteorology.">Following requests from the aviation industry, the Bureau of Meteorology changed the format of Area Forecasts (ARFORs) from text based to graphical on 9 November 2017. The new format is known as a Graphical Area Forecast (GAF). More information regarding GAFs is available from the Bureau of Meteorology.
While stringing powerlines to the Carrapateena mine about 60km east of Woomera Airfield, South Australia, Airbus Helicopters AS350B3e Écureuil (Squirrel) registered VH-SZS, pulled draw wire towards pole 164. Witnesses observed the aircraft traverse slowly up the gradient of rising terrain towards the pole in a near backwards attitude toward the morning sun and in the presence of substantial dust. As the aircraft approached the pole it was observed to continue to fly in a controlled manner until it collided with the pole and fell to the ground.
Site and wreckage examination did not identify any aircraft defects or anomalies that might have contributed to the accident. The recorded engine data also showed no anomalies with the engine prior the impact with the pole. Additionally, no evidence was found to suggest any medical, fatigue related or physiological issues that would have affected the pilot’s performance on the day of the flight. Therefore, this analysis will focus on the operational and environmental factors that led to an experienced helicopter pilot inadvertently colliding with a known obstacle.
Development of the accident
Altered methodology
The pilot received 7.2 hours of training in helicopter powerline stringing in the 3 days of the first tour between 5 February and 7 February 2019. By the third tour (March 10-11) video and photographs taken of the stringing operations showed that the pilot had altered the methodology from that which was taught. Witnesses on the day of the accident also described the same modified method being used. The new method placed the helicopter at a lower operating height above the ground, in a tail-rear attitude, while tracking out to one side before climbing around the pole.
It is not known when exactly the pilot began altering the stringing method, only that it was in use during the third tour and on the accident day. It is therefore likely that the pilot had successfully strung dozens of poles using the new method before the accident, possibly re-enforcing the validity of the method to the pilot.
Span length
By 20 March, the pilot had strung 122 poles (almost all of which were strung 3 times). The length of these spans varied from 156 m to 351 m. The vast majority (85 per cent) of the spans were between 200‑300 m in length, with the average being about 250 m. The accident span was 174 m, one of the shortest of the 122 the pilot had done. Only 4 spans were shorter, and they were all strung on March 10, 10 days prior to the accident. Additionally, the span immediately prior to the accident was 253 m. The accident span was nearly 80 m shorter than the average span, and 79 m shorter than the penultimate span. Based on the pilot’s previous experience, it is possible the pilot’s expectation was that pole 164 was still some distance away at the time on the collision. Compounding this risk was the gradient of the accident span. With an elevation gain of 12.86 m, the span between poles 163 and 164 had the greatest gradient of any the pilot had flown at Carrapateena.
Visibility of pole 164
A feature of the taught stringing method was that both the recently strung pole and the next target pole are both visible at all times. Maintaining a straight-line path between the poles with the aircraft at 90° (sideways) to the relative track ensures visibility of both poles is maintained. The method also places the aircraft at an altitude higher than the target pole, therefore safeguarding against collision. The pilot’s altered methodology placed the helicopter both at lower altitude and in a pronounced tail-rear attitude.
The low altitude exacerbated the amount of dust in the air around the helicopter. Witnesses described a plume of dust higher than the nearby poles. Although the perspective of observers on the ground may not accurately represent that of the pilot, it is clear from observations and photographs taken on the day (Figure 4), that there was significant dust in the vicinity of the helicopter as it approached pole 164.
Analysis of the sun position and observations made on site indicated that the sun would have been in the general direction of the pilot’s vision of pole 164. Although the pilot was wearing a helmet mounted visor at the time of the accident, sun glare, particularly in combination with dust, may have reduced visibility of the pole.
Additionally, several witnesses, as well as photographs, show that the helicopter was being flown in a near backwards attitude as it traversed towards pole 164. Although it is difficult to determine the exact proportional effect of each element in isolation, it is likely that in combination, the near backwards attitude of the aircraft, significant dust and the position of the sun would have led to a reduction of the pilot’s visibility of pole 164 and the ground. In the absence of visual cues of the pole it is likely that the pilot’s situational awareness of pole 164 was degraded leading to the pilot inadvertently colliding with it.
Supervision
The operator did not have any documented requirements for supervision after the pilot was signed-off for powerline stringing, nor were they required to by regulations. Despite this, after the chief pilot left Carrapateena on 7 February 2019, they were in contact with the deputy chief pilot by telephone several times to check-in and see how the job, and the pilot, were going. Unfortunately, this indirect supervision relied either on the pilot being aware there was a problem with their methodology, or the pilot disclosing that they had intentionally altered the methodology.
The investigation could not determine why the pilot modified the stringing methodology. It is possible it was a result of an unperceived degradation of a newly taught skill, or the intentional modification of the technique. In either case, it is highly likely that ongoing supervision by an experienced powerline stringing operator would have identified the modified methodology and the associated risks.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the Collision with terrain involving Airbus Helicopters AS350B3e, VH-SZS 60 km east of Woomera Airfield, South Australia, on 20 March 2019.
Contributing factors
The pilot was using a stringing technique that was different to that instructed by the chief pilot. The modified method resulted in the aircraft operating at a lower height above the ground, which led to the pilot colliding with pole 164.
Due to a combination of the attitude of the aircraft, dust and the position of the sun, it is likely that the pilot lost situational awareness of pole 164, leading to the collision with it.
Other factors that increased risk
There were no requirements in Aeropower procedures to provide any post-training supervision for powerline operations. What supervision was provided was ineffective in identifying that a modified stringing method was being used by the pilot. [Safety issue]
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: There were no requirements in Aeropower procedures to provide any post-training supervision for powerline operations. What supervision was provided was ineffective in identifying that a modified stringing method was being used by the pilot.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Aeropower Pty. Ltd.
OZ Minerals
ElectraNet
Civil Aviation Safety Authority
South Australian Police Service
Bureau of Meteorology.
Airservices Australia
accident witnesses
video footage and photographs of the accident flight and other photographs and videos taken on the day of the accident and prior to the accident.
recorded data from the Engine Data Recorder unit on the aircraft.
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
Civil Aviation Safety Authority
Aeropower Pty. Ltd.
The chief pilot
OZ Minerals
Ventia
Powerlines Plus
ElectraNet
BEA
Submissions were received from the Civil Aviation Safety Authority, Aeropower, the chief pilot and OZ Minerals. The submissions were reviewed and where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Occurrence summary
Investigation number
AO-2019-015
Occurrence date
20/03/2019
Location
Pernatty Station, 60 km east of Woomera Airfield (Carrapateena Mine)
On 28 January 2019, at 1908 Eastern Daylight-saving Time,[1] a Sikorsky S-64E Skycrane, registered N173AC and operated by Erickson Inc., collided with water at Wood Creek Dam, Victoria. The collision occurred following an approach to the dam to fill an external tank with water for firebombing operations. All the crew exited the aircraft and swam to shore. One crewmember was seriously injured and two were uninjured. The aircraft was substantially damaged.
What the ATSB found
The ATSB found that the approach path to the dam was incrementally shortened over the course of the days’ operation. It is likely that the final tight approach path was at the upper margins of allowable speed and angle of bank, requiring a steep flare that contributed to the aircraft entering vortex ring state on approach.
Furthermore, the shape of the dam and surrounds of the site reduced the opportunity for recovery, and the aircraft impacted the water. The carriage of additional crew increased the risk of injury, while training for emergencies directly supported the crew’s survival.
What's been done as a result
Erickson Inc. advised that the following safety action was taken in response to this occurrence:
vortex ring state avoidance and recovery was to be emphasised in future training and checking
a policy preventing non-essential personnel from being aboard during firefighting operations had been introduced.
In addition, the organisation that facilitated operation of the United States‑registered Skycrane during Australian firebombing operations, Kestrel Aviation, advised that the following safety action was also undertaken:
It was reiterated to pilots that, though aircrew work in close partnership and cooperation with aerial attack supervisors (AAS), AAS instructions are advisory. The pilot in command retains full authority to make decisions to ensure the safety of the aircraft and management support was available if escalation was required.
Kestrel Aviation increased the frequency of contact with Erickson Inc. crews to provide safety management support, and reduce operational pressure.
Safety message
When performing aerial work it is easy to accept incremental changes that gradually reduce margins. While these changes often increase efficiency, it is worth checking how much an operation has deviated from earlier versions and re-evaluating elements if they appear less stable.
Helicopters excel in confined areas, yet are vulnerable when operating within them. Periodic reassessment of confined areas, and approach and departure profiles, should be done throughout the duration of an operation. Both supervising parties and operating crews are well-positioned to do this.
Following an accident, it is common to overlook the need to unplug one’s helmet. Using a good quality extension cable that will maintain the integrity of communications and release under tension in the event of an emergency can also save lives.
On 28 January 2019, a Sikorsky S-64E Skycrane, registered N173AC, operated by Erickson Inc., was prepared for firebombing flying activities at Essendon Airport, Melbourne, Victoria. The Crew Chief, a licenced aircraft maintenance engineer, confirmed the aircraft’s serviceability and readied it for flight.
The crew of N173AC comprised three specialists:
Pilot in Command (PIC), handling the aircraft and managing the task
Second in Command (SIC), supporting the PIC with operational calculations and monitoring
Crew Chief, voluntarily supporting the crew in flight with systems knowledge, and keeping a lookout for obstacles behind the aircraft, from a rearward‑facing seat.
The crew were highly experienced in S‑64 firebombing operations. The PIC had eighteen years’ helicopter experience and had operated the S-64 for four years. The SIC had forty-four years’ helicopter experience, twenty years flying S-64, and had been firefighting in Australia for twenty years. The Crew Chief had thirty-four years’ experience in helicopter engineering, including twenty-six years maintaining and developing the S-64.
All the crew reported that they were acclimatised and well-rested. Both pilots acted as alternating PIC and SIC in two-hour cycles throughout the day. The PIC sat in the left seat, and the SIC in the right. The pilots exchanged positions and roles prior to the beginning of each cycle. The accident occurred on the third cycle of the day.
At about 1000 Eastern Daylight‑saving Time,[2] the crew repositioned the aircraft to Latrobe Valley Airport, 125 km east of Melbourne. There, they rested and prepared the aircraft while awaiting further instructions. After lunch, the crew was tasked with firebombing activities to the west of Thomson Dam, Aberfeldy, Victoria (Figure 2).
An aerial attack supervisor (AAS) coordinated the aerial assets for the firefighting mission. The AAS identified a dip site.[3] The considerations for selection of the dip site included:
no obstacles or wires
that the site would remain clear of smoke
the distance from the flame front allowing efficient delivery of suppressant
aircraft working in concert could fill and drop their load while maintaining safe separation from each other.
Once the AAS identified the dip site, they showed the firebombing crew its location. The firebombing crew then had the final say on the dip site’s suitability for the operation.
Figure 2: Dip site location (Fire boundary as of 31 January 2019)
Source: Country Fire Authority
The dip site was Wood Creek Dam, 7 km west of the fire front. It sat at 3,480 ft above mean sea level, at the eastern base of Mount Gregory, in the Yarra Ranges National Park, Victoria (Figure 3). It had a narrow body and steep sides surrounded by tall trees. The crew assessed the dip site as confined, but not outside acceptable limits of operation.
The flight crew used the Aircraft Weight Reference Guide to calculate how much water the aircraft could carry, and then reduced the calculated figure by 91 kg to optimise performance for departure from the dip site.
Figure 3: The steep sides and narrow body of the dip site pictured from the west
Source: Department of Environment, Land, Water and Planning, Victoria, annotated by the ATSB
The crew used the aircraft’s pond snorkel[4] to fill the tank. The snorkel required the aircraft to be stationary for up to 45 seconds, and a dedicated pump provided the pressure to fill the tank. While there were operating instructions and a checklist, there were no specific procedures around approaching waterways with a pond snorkel.
The operator classified firebombing as an external load operation, since the suppressant can be jettisoned. Procedures for control of the aircraft during external load operations required:
descent with any combination of airspeed and rate of descent as long as rate of descent was below 800 ft/min when below 200 ft above ground/water level
landing with a nose-up attitude of less than 10° in order to avoid tail skid strike
limiting angle of bank to 30° for safe operation when the Automatic Flight Control System (AFCS) was engaged
AFCS to be engaged in normal operations in order to smooth pilot inputs
minimum clearance to obstacles of half a main rotor diameter (11 m for the S‑64).
During filling, the helicopter was positioned one main rotor diameter from the left-hand side of the dam for the PIC to keep visual hover references. This left no more than two rotor diameters to the right.
On each fill, the crew flew a descending right turn, stopped in a high hover, then descended vertically into the dam. Satellite data showed early approaches had a final approach length of 300 m to 400 m. As the aircraft crossed the southern tree line of the dip site, airspeed averaged 30 kt, and the rate of descent averaged 630 ft/min.
After a number of water drops, the AAS re-tasked the crew to fight a flame front further north, which was east-northeast from the dip site. Each drop was also incrementally further north. This resulted in the crew gradually tightening the approach to the dip site (Figure 4).
Figure 4: Change in working location over time
Source: Google Earth, Kestrel Aviation, annotated by the ATSB
During the occurrence approach, the tighter approach resulted in a greater than normal flare[5] to arrest the aircraft at the aiming point in the dip site. The higher nose pitch up prompted the SIC to advise the PIC to move forward of the trees before descending any further to ensure tail rotor clearance. Clear of the trees, the flare was increased.
While descending with a nose-high attitude, the aircraft struck the water tail-first, submerging and removing the tail rotor, causing rapid rotation to the right through one and half turns. While rotating, the main rotor blades separated as they contacted water. The right cockpit door separated from the fuselage, and the aircraft came to rest on its left side, submerging the cockpit.
Each crewmember recalled the rehearsed drills from their helicopter underwater escape training (HUET). They identified their seat belt and nearest exit to orientate themselves in the aircraft. They all waited until the last moment to draw a breath, and did not unbuckle and exit the helicopter until motion had ceased. The crew reported that it was not possible to see anything underwater, and that jet fuel contamination was present.
The SIC in the right seat exited through his doorway, from which the door was already missing. The PIC could not open his door so he swam across the cabin (up) and was assisted by the SIC to exit through the right hand door. As the rear door was jammed, the crew chief in the aft seat pushed out a window from the rear of the cabin, and exited through it.
Neither pilot unplugged their helmet. However, the extension cords from the aircraft to the helmet plug allowed the plug to release, preventing the helmets from snaring the pilots. All three crew escaped, and inflated their life jackets. Two crew were uninjured, and one crewmember sustained a knee injury.
At the time of the accident, crews aboard S-76 and S-61N helicopters were assessing the potential of the dip site for later use in night operations. An AAS aboard the S-76 relayed details of the accident to an incident controller who enacted the emergency response plan. Neither the S-76 nor the S-61N was equipped or able to provide direct assistance, other than monitoring, and relaying information.
Following exit from the helicopter, the only form of communication available to the Skycrane crew was hand signals. They gave thumbs-up indications to the crew of the overhead S-61N to advise that they were okay. The Skycrane crew then swam to shore and trekked through dense bush to a road where they were met by rescuers.
Meteorological information
The crew received a situation report, including weather and a common barometric pressure[6] as they began the firefighting activity. Following the failure of a 4G-equipped iPad earlier in the day, beyond this report, the crew did not have access to up-to-the-minute weather data.
The weather on the day saw temperatures over 25°C, a significant reduction from recent heatwave conditions. Winds aloft were northerly and pushed plumes of smoke to the south. The crew and witnesses to the event all assessed the wind to have been a northerly. The crew of the Skycrane advised that the wind had dropped off from around 16 kt and remained a light northerly.
Turbulence was reported to be mild. Outside of smoke, visibility was greater than 10 km. At the time of the accident, the sun was at 258°, and 15° above the horizon.
Locations on the ground showed significant local variation in wind direction and strength throughout the day (Figure 5).
Figure 5: Local variation in wind speed and direction. (15-minute average 1900 to 1915)
Source: Google Earth, Wunderground, Bureau of Meteorology, annotated by the ATSB
Flight recorders
It was a contractual requirement that all firefighting aircraft were equipped with satellite tracking devices. That data was stored remotely from the aircraft and was available shortly after the accident. The system recorded the location, altitude, heading, and groundspeed of the aircraft at 15‑second intervals for the duration of operation.
The Skycrane was also fitted with a Universal Avionics CVR-120 cockpit voice recorder (CVR). Divers recovered the CVR 45 days after the event, once the complex task of recovering the helicopter allowed access to the device. The CVR, submerged for the duration, showed little outward damage, yet voice data could not be recovered from the unit.
Vortex ring state
Vortex ring state (VRS) is a condition of powered helicopter flight that causes a loss of lift in the rotor system. During normal operation, the rotor system pushes large amounts of air down while it produces lift. If the helicopter descends into this downwash, the air can recirculate back up and over the rotors instead of it flowing down and away. This causes the same parcel of air to circulate around the rotor. As a result, the rotor system no longer has the steady stream of air required to produce lift and the helicopter will descend despite the application of additional power.
The United States Federal Aviation Administration Helicopter Flying Handbook details the methods of VRS recovery as follows:
The traditional recovery is accomplished by increasing airspeed, and/or partially lowering collective to exit the vortex. In most helicopters, lateral cyclic thrust combined with an increase in power and lateral antitorque thrust will produce the quickest exit from the hazard. This technique, known as the Vuichard Recovery (named after the Swiss examiner from the Federal Office of Civil Aviation who developed it) recovers by eliminating the descent rate as opposed to exiting the vortex.
The crew were trained to use the Vuichard recovery technique for recovery from vortex-ring state. In the Skycrane, it requires the pilot to apply full power, right cyclic[7] and left pedal to side slip the helicopter out of its own downwash and into the ascending air just outside of the rotor system.
Safety analysis
Shortening of approach and vortex ring state
The sun progressed to a point low in the west, opposing the crew’s turn onto final approach, and casting long shadows from the steep sides, across the tree line and the surface of the dam. The crew reported that from their angle of approach the surface looked glassy, supporting their assessment of the wind becoming lighter. Video recorded shortly after the event showed that the shape of the dip site and shadows disguised a light tail wind. Wind was only visible on the surface through a 10-degree arc from the south-southwest.
A witness to the event reported that the aircraft had an apparent high rate of descent and a nose‑high attitude. The crew reported that they did not feel that any of the parameters were excessive, though speed and angle of bank were felt to be at the higher end of their normal range.
The satellite data showed the accident approach was a right-hand turn, with about a 30° angle of bank, and a radius of 150 m. The rate of descent developed from 650 ft/min to 780 ft/min. All flight parameters were within operational limits, however the length of the final approach was considerably shorter than earlier approaches (Figure 6).
The shorter approach at the upper end of the acceptable envelope of operation required a steeper than normal flare to stop the helicopter. The crew reported that once they descended below the tree line, the aircraft generated no lift and fell into the dip site, colliding with water. The crew stated that they had very likely encountered vortex ring state (VRS). The topography, high rate of powered descent, and steep flare that reduced the airspeed, created conditions conducive to the onset of VRS. The crew reported that the rapidity of onset and dimensions of the dip site did not provide enough time or space to manoeuvre sideways to effect a recovery.
Figure 6: Shortening of final approach path
Source: Google Earth, Kestrel Aviation, annotated by the ATSB
Carriage of additional crew
The operator’s operations manual stated that only flight crew and crew essential to the operation could be carried aboard the aircraft during firefighting operations. The operation could be conducted without the Crew Chief and not all company Crew Chiefs were on board their aircraft during firefighting operations.
While the Crew Chief had significant system and task knowledge, he was not required to be on board the helicopter. On this occasion, his presence exposed him to the significant hazards associated with underwater egress. More generally, the carriage of additional personnel during specialised operations like firefighting exposes them to unnecessary risk.
Egress from the submerged helicopter
Although two other helicopters were overhead, and their crews had activated the emergency response, no immediate assistance was available to the Skycrane crew. The crew had to rely on their own resources and equipment to survive.
The crew reported that Helicopter Underwater Escape Training (HUET) was fundamental to their survival. HUET enabled the crew to act rationally and decisively when submerged in the cockpit and to use the regularly‑practiced drills to escape the aircraft.
Additionally, the helmet cord release mechanism (Figure 7) prevented snaring and potential drowning after the pilots exited the submerged aircraft without unplugging their helmets.
Figure 7: Helmet cord release mechanism
Source: ATSB
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The crew conducted a tight descending right hand turn into the dam, inside the upper margins of the flight envelope. This approach required a steep flare on arrival and likely resulted in the rapid onset of vortex ring state.
The dam’s steep sides and narrow tapered body provided limited opportunity for vortex ring state recovery actions, contributing to collision with water.
The Crew Chief's presence aboard the aircraft during firebombing operations exposed him to unnecessary risk.
All crewmembers credited their survival to skills learned and practiced in Helicopter Underwater Escape Training. In addition, the helmet cord extension cables detached easily from the aircraft, contributing directly to the crew's egress from the flooded cockpit.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 19 January 2019, a Eurocopter EC130 helicopter, registered VH-YHS, conducted a private flight from Moorabbin Airport to an authorised landing area (ALA) near Mansfield, Victoria with the pilot and two passengers on board. A return flight to Moorabbin was planned for later that afternoon.
At about 1500 (Australian Eastern Daylight Time - AEDT), the pilot and passengers boarded the helicopter at the ALA for the return flight. The pilot prepared for take-off and lifted off the helicopter more rapidly than he normally did. As the helicopter became airborne, it began to rotate counter-clockwise (yaw to the left). The pilot tried to control the yaw but the helicopter quickly turned through 360° and, unable to control it, he made a decision to land the helicopter.
The left skid of the descending helicopter subsequently contacted the ground, resulting in a rolling movement that led to the main rotor blades striking the ground. The collision destroyed the aircraft, the pilot sustained minor injuries however the passengers were uninjured.
What the ATSB found
The investigation did not identify any airworthiness issues with the helicopter and it was considered that the loss of control was not attributable to a mechanical issue. It was also determined that the prevailing light winds did not contribute to the loss of control.
The pilot reported that he did not lift the helicopter into a balanced hover, and tried controlling its yaw mainly with the cyclic control instead of through the full application of opposing right, tail rotor pedal. Management of unanticipated yaw in helicopters with shrouded tail rotors (Fenestron) is the subject of the manufacturer’s guidance and learnings from similar accidents.
Safety message
This accident demonstrates the criticality of helicopter pilots understanding the aircraft’s characteristics so that they can anticipate its response when becoming airborne, and are not surprised by events. Controlling yaw in helicopters with a Fenestron tail rotor, as in this case, is an important consideration. Airbus Helicopters and the European Union Aviation Safety Agency (EASA) provide specific guidance relating to this issue to assist pilots.
The occurrence
What happened
At 1033 Eastern Daylight‑saving Time[1] on 19 January 2019, a Eurocopter EC130 helicopter, registered VH-YHS (YHS), departed Moorabbin Airport for a private authorised landing area (ALA), 19 km south-south‑east of Mansfield, Victoria. The pilot and two passengers were on board for the private flight to a rural property and intended to conduct a return flight that afternoon. The pilot’s pre-flight inspection had not identified any defects or outstanding maintenance issues for the helicopter.
At 1115, after an uneventful flight, YHS landed at the rural property. Over the next few hours, the pilot attended to various matters there as planned, and had lunch with the passengers.
Shortly before 1500, the pilot and passengers returned to the helicopter. The helicopter was parked in an open area, facing south with a 0.5 m-high earth mound to its left (Figure 1). The mound prevented water entering the nearby shed and ran the length of the area, which had clusters of trees around it in different directions. The pilot had undertaken five previous flights to the property in the helicopter in the previous 5 months.
After assisting the passengers to board the helicopter, the pilot conducted a walk-around and did not identify anything unusual. He then boarded and, following a normal engine start, carried out his take-off checks. As was his usual practice, he set the friction settings for both the cyclic[2] and collective[3] controls to minimum resistance.[4] The wind was about 10 kt from the south-west (about 45° to the right of the helicopter), the sky was clear and it was approximately 30º C.
As the pilot increased to full power for take-off, he observed that the front right passenger had not put on her headset and signalled for her to do so. While he waited for her to put the headset on, keeping YHS on the ground, he noticed the cabin temperature was 32 ºC and turned on the air‑conditioning.
Shortly after 1500, the pilot was again ready to take-off. He raised the helicopter off the ground, more rapidly than he normally did without getting the usual ‘fine balance’[5]. At a height of about 3 m above the ground, the helicopter began to yaw to the left (turning counter-clockwise), seemingly pivoting about the tail and its attitude became progressively unstable (Figure 1, Top).
The pilot applied inputs, mainly cyclic, to control the helicopter’s movement but the yaw increased. The aircraft now seemed to be pivoting about the main rotor, moving closer to the trees and shed (Figure 1, Middle). The pilot recalled that the helicopter felt ‘unstable’ and moved the cyclic but did not get the response he expected. In seconds, the helicopter had turned through 360° (Figure 1, Bottom). Unable to control the helicopter, the pilot decided to land and lowered the collective.
As the helicopter descended, its left skid contacted the mound, resulting in the helicopter pivoting around that skid and the main rotor blades striking the ground. The helicopter came to rest on its left side, facing the shed (Figure 2). The sequence, from lift-off to ground contact, occurred over about 5 seconds.
The pilot turned off the engine and battery, exited through the shattered left windscreen and assisted the passengers from the helicopter. The pilot sustained minor injuries while the passengers were uninjured.
Figure 1: Accident sequence
Source: ATSB analysis of information from pilot and witness video (partial) superimposed on Google Earth image
Figure 2: Accident site
Source: Seven News Melbourne, annotated by ATSB
Pilot
The pilot completed his helicopter flight training in a Hughes 300 helicopter in 2010. He completed EC130 type training in November 2011 and had accumulated 227 flight hours in that aircraft (from a total of 315 flight hours). Since his last flight review in November 2017, he had flown YHS for 13.5 hours of which 4 hours had been in the 90 days preceding the accident – the last flight being 46 days prior.
The pilot commented that he had:
not heard or seen anything unusual with the helicopter before the accident
tried controlling the yaw mainly with the cyclic, did not know how much right pedal he had used and assessed that he should have used more pedal to control yaw
not flown regularly since his last flight review and noted that during his EC130 type training he had needed more pedal input than in the Hughes 300.
Aircraft information
The EC130 is a single-turbine engine helicopter with a clockwise-turning main rotor and a shrouded Fenestron tail rotor (Figure 2). The helicopter has a maximum take-off weight of about 2,427 kg and can carry seven occupants. The EC130 is a high-performance helicopter compared to the Hughes 300 (in which the pilot first trained). The Hughes 300 has a counterclockwise turning main rotor and a conventional unshrouded tail rotor.
The EC130 with its Fenestron anti‑torque system[6] requires greater right pedal[7] input to overcome torque from the main rotor during lift off than a helicopter with a conventional tail rotor. The pedal control inputs are also not linear with respect to the effect on helicopter yaw.
The helicopter’s manufacturer (Airbus Helicopters) published service letter 1673-67-04 in February 2005 with guidance for managing yaw. The letter reminded pilots that the Fenestron anti‑torque system requires more right pedal travel than a conventional tail rotor to counter left rotation (yaw). The letter stated that if sufficient pedal is not applied quickly to correct yaw, its rate will increase. Further, insufficient pedal input to stop yaw combined with pilot input to decrease altitude could result in the helicopter rolling to the side and contacting the ground.
Post-accident activities
There was no recorded data to determine the flight control inputs and their effect on the motion of YHS during the accident. The pilot’s account, a partially obscured witness video, and photographs of the wreckage were the main sources of evidence.
The maintenance organisation for YHS carried out an examination at the accident site before moving the wreckage to its maintenance facility. This examination found no evidence of airworthiness issues that could have resulted in the accident. It was also determined that the helicopter was within its performance envelope and had sufficient fuel for the planned flight.
The ATSB sought the manufacturer’s input for this accident and was advised that as no technical (mechanical or control) issues with YHS had been identified by the maintenance organisation, the accident was probably the result of a handling error.
In July 2019, about 6 months after the accident, Airbus Helicopters published safety information notice 3297-S-00 to highlight unanticipated yaw. The notice warned that an unanticipated yaw can be rapid and is most often toward the left (where the main rotor rotates clockwise). It further noted that even if the pilot’s response was prompt, the yaw might not immediately subside and lead to the pilot thinking that the input was ineffective.
Similar accident
In October 2015, an EC130 helicopter was departing Megève altiport, France, for a sightseeing flight when the pilot lost control of the aircraft, which collided with the ground (BEA2015-0647 report). The helicopter was destroyed, and the seven occupants were injured.
The pilot had 300 flight hours in helicopters, including 9.5 hours in an EC130 and 74 in the similar AS350 helicopter. The investigation found that while stabilised in the hover, the pilot initiated a left turn to face the climb out direction. However, the pilot was unable to stop or slow the yaw and decided to land, lowering the collective. The helicopter yawed through several more revolutions before colliding with the ground. No technical issues to explain the accident were identified.
As part of the investigation, a flight in a helicopter of the same type in similar conditions was undertaken, and it was found that pushing the right pedal to 70 per cent of its travel stopped a yaw rate of 100° per second to the left in 3 seconds.
Safety analysis
The earlier flight made by VH-YHS (YHS) that day indicated the helicopter was operating normally with no defects. The high-performance helicopter was also operating well below its maximum capacity with only three occupants.
In preparing to take-off, the pilot lifted YHS more rapidly than he normally did without first letting it rest lightly on the skids and applying control inputs to lift it gently into a balanced, controlled hover for the climb out. The higher-than-normal application of control inputs resulted in the torque from the main rotor not being balanced by the anti-torque from the Fenestron tail rotor. Consequently, once the helicopter was off the ground it yawed significantly to the left. The wind from the right may also have initially increased the yaw rate.
The pilot’s pre-take-off checks did not confirm that everyone and everything was ready for the flight. As a result, he had to delay the take-off while a passenger put on her headset. He then noticed the elevated temperature and turned on the air-conditioning. These interruptions may have influenced his actions in lifting off more rapidly than he normally did.
The rate of left yaw offered limited time to regain control. The pilot reported that he principally applied cyclic control rather than the required full application and maintenance of opposing right, tail rotor pedal input. When his applied inputs did not arrest the yaw rate, the pilot assessed that the best option was to land the helicopter.
Similar accidents in the same or comparable helicopters, together with manufacturer’s guidance, provide information for pilots to manage unanticipated yaw and avoid accidents. These show that the outcome of YHS’s attempted landing with a significant yaw rate was somewhat predictable - a skid contacting the ground, the helicopter rolling over and the main rotor blades striking the ground. The rapid development of the accident sequence (about 5 seconds) also illustrates the limited time for pilot actions/decisions in such hazardous situations, which fortunately did not result in serious injury in this case.
The maintenance organisation’s examination found no evidence of airworthiness issues with YHS to explain the accident. The pilot’s account and the manufacturer’s comments also support a conclusion that a mechanical issue and the light wind did not contribute to the accident.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
The pilot was unable to control VH-YHS yawing to the left after lifting off and decided to land. When the left skid of the descending helicopter contacted the ground, it rolled over and the main rotor blades struck the ground, destroying the aircraft with the pilot sustaining minor injury.
No mechanical issue with the helicopter was identified and the prevailing light wind did not contribute to the loss of control and subsequent collision.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
At about 0825 Eastern Standard Time on 9 January 2019, an Insitu ScanEagle X200 (X200) unmanned aircraft system was launched to conduct ‘beyond visual line of sight’ aerial survey work in the Woleebee Creek area of Queensland. The flight crew consisted of two pilots and two ground crew.
Shortly after launch, one of the ground crew observed the X200 pitch up and then enter an aerodynamic stall. The flying pilot commenced the emergency procedures for a stall-spin, however the X200 self-recovered before the checklist was completed. At about the same time the pilots received an alert indicating an airspeed sensor failure and initiated the associated emergency procedure checklist.
Before visual sight was lost, the ground crew observed the X200 oscillating in pitch as it continued to fly to the programmed first waypoint. While the flying pilot was executing the emergency procedures checklist, the X200 entered a second aerodynamic stall. Following self‑recovery from a low height above terrain, the X200 commenced a climbing orbit. Shortly after, the X200 entered a third aerodynamic stall, this time from a height that was insufficient for recovery, and collided with terrain. There was no post-impact fire and the X200 was destroyed. There were no reported injuries to people or damage to infrastructure. A post-incident inspection of the X200 identified a partial blockage in the pitot system.
What the ATSB found
The investigation found that the blockage in the pitot-static system resulted in unreliable airspeed data being supplied to the autopilot. Unreliable airspeed data led to the X200 entering an aerodynamic stall at a height that was insufficient for recovery.
During the pre-flight checks, there were opportunities for the erroneous airspeed indications to be identified. However, they were not recognised by the crew or flagged by the ground control station.
What's been done as a result
Following the occurrence, the manufacturer revised their procedures to reduce the risk of aircraft being affected by a pitot blockage. Additionally, all of the operator’s pilots underwent refresher training. This included emergency procedures simulator experience.
The X200 manufacturer revised their procedures to provide support to pilots and ground crew in correct assembly of the articulated turret, identifying anomalies (on the ground and in-flight), and steps for aircraft recovery in the event of a departure from normal flight. In addition, updates to the operational software would ensure any spurious on‑ground anomalies were alarmed, to prevent the X200 being launched with an unidentified issue.
Safety message
This occurrence highlights the importance of confirming the significance of any unexpected observations during the pre-flight checks, to minimise the risk of the aircraft departing with an unserviceability. In addition, providing pilots and ground crew with the reasoning behind specific checks and procedures can enhance their ability to identify anomalies and perform the appropriate corrective actions in a timely manner.
Insitu ScanEagle X200
Source: Insitu Pacific
The occurrence
What happened
On the morning of 9 January 2019, the Insitu Pacific (the operator) crew prepared to conduct a 4‑hour ‘beyond visual line of sight’ survey flight, in the Woleebee Creek area, about 350 km west‑north‑west of Brisbane, Queensland. The flight was being conducted by an Insitu ScanEagle X200 (X200).
The crew consisted of two remote pilots[1] (one acting as mission controller/pilot in command and one acting as pilot flying) and two ground crew (who were also qualified remote pilots).[2] The two pilots for this flight were located in the ground control station (GCS).[3] Headsets were worn by all crew members, to enable effective communication. All crew reported to being ‘refreshed’ and looking forward to the day’s flight.
The X200 was launched at 0825 Eastern Standard Time.[4] The crew described the launch as ‘textbook’. The secondary ground crew member maintained visual contact with the X200, typically done until advised by the pilots that they had video feedback from the on-board camera.[5] He reported that, about one minute after launch, the X200 pitched up ‘quite high’, before entering an aerodynamic stall.[6] He immediately advised the pilot flying (PF) with the standard phrase ‘wings level, wings level, you’re stalling’. At this time, the primary ground crew member also observed the X200 in a ‘left-hand spin’ and advised the PF ‘you’ve stalled, wings level, wings level’.
At the same time, the GCS identified the stall condition and projected the ‘stall-spin’ emergency procedures checklist to the display. The PF commenced the checklist items, however the X200 self‑recovered before the checklist was completed. The ground crew reported the X200 recovered ‘low to the ground’ and then commenced a climb to return to the programmed flight altitude.
At about the time of the recovery from the first stall, the GCS initiated the warnings and emergency procedures checklist for an ‘airspeed failure’. Upon the mission controller’s direction, the PF commenced the airspeed failure checklist. The ground crew reported that following a ‘steep’ climb, the X200 was then observed to be ‘porpoising’ (oscillating in pitch) while it continued to the first programmed waypoint. Shortly after this, the X200 flew beyond visual sight of the ground crew.
Telemetry data showed that, about 90 seconds after the first stall, the X200 entered a second stall. The X200 self-recovered again, at about 150 ft above the ground, and commenced a climbing orbit. After about 30 seconds, the X200 entered a third stall and impacted the ground eight seconds later. The mission controller advised the ground crew that the X200 had been lost. Total flight time was less than four minutes and distance from the launch site to the collision with terrain location was about 4.75 km (Figures 1 and 2).
Figure 1: X200 flight path
Source: Insitu Pacific and Google Earth, modified by the ATSB
Figure 2: X200 flight profile
Source: Insitu Pacific and Google Earth, modified by the ATSB
Post-accident recovery and inspection
The aircraft impacted the ground near vertically, there was no post-impact fire and the X200 was destroyed. There was no evidence of in-flight break-up or collision with vegetation or infrastructure prior to the impact. In addition, there were no reported injuries. The operator conducted an examination of the occurrence X200 and identified a partial blockage in the pitot system, which was subsequently confirmed by the manufacturer. The blockage appeared to be a combination of a section of O-ring debris and grease.
Flight operations
The Civil Aviation Safety Authority (CASA) issued the operator with an authorisation to operate the X200 beyond visual line of sight, within a defined area. Some of the authorisation’s requirements included:
all remote pilots were to hold a CASA authorisation
a mode C transponder[7] was to be operational, and transmitting accurate barometric altitude, on all flights
a primary and secondary ‘fail safe’ mode to ensure that, in the event of data-link loss, the X200 did not depart the area of operation and would land at a pre-determined location
air traffic control at Brisbane was to be advised of the intended operation 15 minutes prior to launch, and the crew were to maintain standard airspace radio procedures for the duration of the flight
the operator was to ensure a current Notice to Airmen (NOTAM)[8] was active for each operation
the X200 was only to be operated in visual meteorological conditions.
In addition to the CASA authorisation, the operator’s procedures included:
no flight over populous areas
operations were conducted at altitudes intended to avoid agricultural and passenger aircraft.
Remote pilots underwent a 10-week course prior to being endorsed to operate the X200. This course included a theory component and time in the simulator. The pilots recalled that ‘airspeed failure’ was included in the course, however they felt that particular emergency procedure wasn’t focussed on as ‘heavily’ as others.
The accident site was located within the defined operational area, which was in accordance with the authorised requirements.
Aircraft information
The ScanEagle is a small, long-endurance, low-altitude unmanned aerial system (UAS) built by Insitu, a subsidiary of Boeing, and is used for defence and civilian applications (the X200 variant). The X200 (Figure 3) has a wingspan of 3.1 m, a length of 1.6 m, maximum take‑off weight of about 23 kg and a typical cruise speed of 50-60 kt.
The nose module (payload) on the X200 is interchangeable, depending on the type of mission being flown, and was supplied by the payload manufacturer. The payload fitted to the X200 at the time of the occurrence consisted of a camera assembly located in an articulated turret (turret). The camera could be directed through a defined fore/aft arc and the turret rotated through 360˚.
The pilot controls the X200 entirely through the aircraft autopilot from launch until recovery. The aircraft’s flight path is controlled by position, altitude and airspeed commands through the remote pilot station computer (part of the ground control station), which is then sent to the aircraft autopilot. The pilot does not have a control yoke, or equivalent, that links directly or indirectly to the aircraft control surfaces.
Typically, once the X200 has launched, the pilot commands it through a pre-planned sequence of locations and orbits around each location of interest. At the completion of the flight’s activities, the pilot would position the aircraft in preparation for the recovery phase using the same method of control. In this instance, the emergency procedure checklist actions involved the pilot utilising additional X200 autopilot control laws in order to negate the erroneous airspeed information.
Figure 3: X200 with articulated turret
Source: Insitu Pacific, modified by the ATSB
Pitot-static system
The pitot-static system senses ram air pressure through the pitot probe (on the forward face of the payload) and static air pressure through the static ports (on each side of the payload). The two pressures are used to calculate true airspeed (TAS) and barometric altitude (Alt). The autopilot uses this data to calculate the minimum and maximum airspeed in relation to the weight of the X200 and to maintain controlled flight.
The pitot and static tubes for the X200 were routed from the pitot probe and static port through the turret and connected to the pitot-static tubing in the fuselage. If not correctly oriented during assembly, the tubes could become pinched, blocked or damaged with turret operation. Obstructed pitot-static tubes have the potential to cause incorrect TAS and Alt calculations, affecting autopilot operation.[9] In addition, the TAS and Alt indications to the pilots would also be unreliable. The manufacturer alerted X200 operators to this potential condition in November 2017, via both a service advisory and an operational advisory. Damage sustained to the X200 during this occurrence prevented testing for possible turret interference.
The service advisory (SA) provided expanded procedures for pitot and static tube routing and connection, and inspection procedures if an anomaly was identified during pre-flight checks. A review of the X200 maintenance records showed the turret had been installed as per the SA in July 2018. Since then, it had been operated for about 80 hours, without indication of turret interference.
The operational advisory (OA) included:
information about how to identify and troubleshoot different types of incorrect TAS and Alt indications on the ground and in-flight
a pre-flight function test to identify incorrect TAS and Alt indications shown on the ground control station (GCS) program
in-flight emergency procedures to normalise the incorrect TAS and Alt indications and avoid loss of controlled flight.
The function test was to be completed before every flight and the OA provided examples of how anomalies with the pitot-static tubing may appear on the GCS display. Where inspection and routing of the pitot-static tubes did not rectify the anomaly, the turret was to be replaced prior to next flight. The OA procedures had been incorporated into the GCS program at the time of the occurrence.
In addition, the payload manufacturer identified a quality issue with the turret assembly procedures that had the potential to induce a blockage in the pitot system. The operator identified that the occurrence X200 was affected by this quality issue, consisting of excess grease and O‑ring debris forming the pitot-system partial blockage. The X200 manufacturer published procedures to inspect (and, if required, clean) turrets that were in-service and prior to fitment. The operator examined the remainder of their fleet with these revised procedures, with no further occurrences identified.
Pre-flight checks
As part of the pre-flight procedures, the primary ground crew conducted an inspection of the X200 while the secondary ground crew readied the launcher and recovery systems. At the same time the pilots, located in the GCS, conducted their pre-flight systems checks, which included a function test of the pitot-static system (Figure 4). This test included the primary ground crew fitting a sealed clear tube to the pitot probe, which increased pressure in the system and simulated an airspeed indication associated with forward flight (equivalent to TAS). The procedure stated that any reduction in pressure (TAS) indicated on the GCS during the test, equal to or greater than the specified limits, was indicative of a system leak that required rectification prior to flight.
During the test, a slow rise of about 10 kt TAS occurred, while the indicated altitude remained steady. The OA detailed that if the TAS ‘increases slowly without turret movement or pressurisation of the pitot-static system’, this was an indication of a blockage in the pitot-static system. As per the OA, turret movement had the potential to induce a restriction in the pitot system tubing, which could ‘clear’ with subsequent movement. The pitot system was pressurised and the turret was being operated for part of this test and as such, the rise in TAS as a possible indication of a blockage may have been difficult to identify. Following this occurrence, a revised OA amended the criteria for the slow increase in TAS to show ‘at any time’ during the procedure, removing any ambiguity surrounding pitot pressurisation and turret movement during the tests.
With no pitot system leak identified by the pilots, the tooling was removed. At this time, the pilot flying (PF) commented that the TAS was ‘slow to release’ (return to pre-check indication). The primary ground crew member reported that he heard this comment however, he took no action as he wasn’t aware of the significance of this indication. The pilot pre-flight checklist identified that slow to release pressure was indicative of a blockage in the pitot system.
Following completion of the crew’s pre-flight checks, the GCS continued with the system self‑checks, while the crew met outside for a pre-mission brief, as per their standard procedure. During the time the crew were outside, the GCS self-check indicated an anomaly within the pitot‑static system. In this instance, there was an increase over time in TAS, while the Alt decreased. For this indication, the procedures required an inspection of the pitot-static system prior to launch. However, this indication was not flagged or latched.[10] Therefore, when the pilots returned to the GCS, there was nothing to alert them to this additional indication of a pitot system anomaly.
Figure 4: Pitot pressure test indications
Source: Insitu Pacific, modified by the ATSB
All subsequent pre-flight checks were described as normal. Weather conditions at the time were recorded as overcast conditions, 22˚C, a wind speed of about 6 kt and were described by the crew as ‘ideal’.
Autopilot and the occurrence flight
The X200 autopilot control loops rely on airspeed to control altitude. The target airspeed for the occurrence flight was 53 kt. Recorded data shows that following launch, the TAS reached 70 kt. This resulted in the autopilot commanding a rapid pitch up to try to arrest the perceived high TAS. The pitch attitude was too great for the actual airspeed, which resulted in the X200 entering an aerodynamic stall. Stall recovery took 12 seconds, with an altitude loss of 579 ft (at a rate of 48 ft/s), before the X200 began to climb back to the programmed flight altitude.
Erratic TAS is one of the parameters that can lead to a stall-spin in the X200. Flight data showed that erratic TAS was present from launch, before the turret was unlocked and operated. This was consistent with a blockage of the pitot system, rather than turret interference.
The erratic TAS also resulted in the porpoising flight profile following the first stall and recovery. Following about 80 seconds of porpoising flight, the data showed another rapid increase in TAS. The autopilot likely commanded the X200 to increase pitch attitude, which again resulted in an aerodynamic stall and rapid reduction in height. Within 12 seconds, the X200 had again self‑recovered from the stall, but at a much lower altitude than the first recovery. The second stall required 778 ft for self-recovery (at 64.83 ft/s rate of altitude loss).
This was followed by another extreme increase in TAS, leading to the third stall. This stall was at a similar rate to the second stall. Recovery was again initiated but only 591 ft was available and the X200 collided with terrain, about 9 seconds later (Figure 5).
Figure 5: Flight data showing erratic indicated airspeed and altitude
Source: Insitu Pacific, modified by the ATSB
Safety analysis
Following launch, the Insitu ScanEagle X200 (X200) twice entered an aerodynamic stall and self‑recovered. The X200 entered a third stall, this time at a lower height, and did not recover prior to collision with terrain. The analysis will examine the pre-flight indications of the pitot system blockage and its effect on the flight.
Pre-flight checks
The pre-flight checks provided three opportunities for anomalies in the pitot static system to be detected. There was a slow rise in TAS, which was indicative of an anomaly in the pitot system. The pressurisation of the pitot system and movement in the turret during the pitot-static function test, however, may have meant that the slow rise in TAS and the physical blockage was not obvious. The slow reduction in TAS after the pressure test was an indication of a pitot system blockage. This was noted by some of the crew, however the significance of this indication was not recognised.
The ground control station (GCS) system self-checks showed an additional indication of a pitot system anomaly, however it was not observed by the crew, as they were carrying out other duties at the time. At the completion of the self-checks, there was no ‘flag’ or other indication on the GCS that the pitot system irregularity had occurred. This resulted in the indications of pitot system anomaly not being identified by the crew or flagged by the GCS, resulting the X200 being launched with a blockage in the pitot system.
Unreliable airspeed data
The X200 autopilot uses true airspeed (TAS) and altitude (Alt) data to maintain controlled flight. The blockage in the pitot system resulted in unreliable airspeed data being provided to the autopilot, affecting calculation of TAS. While there remained the possibility that the turret interference may also have been present, it could not be determined as contributory in this occurrence. Flight data showed that erratic (TAS) data was present from launch, before the turret was unlocked and operated. Subsequent movement of the turret may have alleviated any turret‑induced restriction in the pitot system but due to the presence of the identified blockage, the airspeed data was unreliable even without any turret interference.
Following launch, the autopilot interpreted the TAS as increasing and increased the pitch (nose up) to maintain target airspeed. This resulted in the X200 nose-up attitude being too great for the actual airspeed and led to an aerodynamic stall. The X200 self-recovered and recommenced the climb to operating altitude.
Following recovery from the first stall, flight data showed the TAS was oscillating by up to 30 kt, resulting in the ‘porpoising’ flight profile, indicative of the autopilot trying to maintain controlled flight using unreliable airspeed data. A rapid 30 kt increase in TAS likely led to the autopilot increasing pitch attitude, resulting in the second aerodynamic stall. Again, the X200 self-recovered, however at a much lower altitude. A third rapid TAS increase followed shortly after, leading to the final stall, with insufficient height available for recovery.
Findings
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Erroneous airspeed system indications during the pre-flight checks were not identified by the crew or flagged by the ground control station, resulting in the X200 being launched with an unserviceable pitot-static system.
A blockage in the pitot-static system resulted in unreliable airspeed data being supplied to the autopilot.
Unreliable airspeed data led to the X200 entering an aerodynamic stall at a height that was insufficient for recovery.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
The operator
As a result of this occurrence, the operator advised the ATSB that the following safety actions, in cooperation with the X200 and payload manufacturers, have been undertaken:
Pilot training
Following the occurrence, all of the operator’s remote pilots underwent refresher training with a focus on identification and emergency procedures regarding incorrect true airspeed (TAS) and/or barometric altitude (Alt) indications. The training consisted of theory (including ‘how’ the system works and symptoms of pitot-static blockage) and several hours’ simulator experience of failures and use of emergency procedures. Feedback from the pilots following this training was positive. In addition, the ATSB was advised that the X200 manufacturer will amend the ab-initio pilot training to highlight pitot-static system anomalies and associated pre- and in-flight procedures.
Training and enhanced procedures can provide ‘reasoning’ behind the steps. This can assist pilots and maintainers in their understanding of indications and events, prompting effective actions and timely resolution.
The manufacturer
Documentation and procedures
The X200 manufacturer published a revised Operational Advisory (OA) on 18 February 2019. One amendment in this revised publication was the inclusion of an image from the occurrence X200, showing the Ground Control Station indication for ‘slow to release’ pitot pressure. The criteria for the slow increase in TAS was also amended to ‘at any time’ during the procedure, removing any ambiguity surrounding pitot pressurisation and turret movement during the tests.
In addition, the revised OA included an additional caution (in red text) warning that the ‘TAS error exceeds launch limit alarm is disabled for pre-flight pitot-static system checks. Therefore, it is critical to monitor the TAS-ALT-Tachometer plot throughout the on ground phase for any abnormal TAS or Alt signatures’. The operator reported that the X200 manufacturer advised a ‘latching system alarm’ would be incorporated into the next software release (scheduled for mid-2019) to alert the crew where the TAS has exceeded a threshold during on-ground checks.
Further, the manufacturer revised their procedures for assembly of the turret and provided a reworked procedure to X200 operators to reduce the risk of in‑service aircraft being affected by a pitot blockage.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 24 November 2018, the pilot and passenger of a Robinson R22 helicopter, registered VH-KZV, were tasked to assist with the recovery of a motor vehicle near Quartz Hill, located about 63 km east-north-east of Ambalindum Station (departure point), Northern Territory. They were also intending to visit some water bore sites.
After departing, they landed at one bore site before continuing towards Quartz Hill. Shortly after entering the MacDonnell Ranges, the helicopter collided with terrain on a downslope (125 km east-north-east of Alice Springs Airport). The pilot was fatally injured and the passenger received serious injuries. The helicopter was destroyed.
What the ATSB found
The ATSB found that the collision with terrain was very likely the result of the helicopter encountering a strong downdraft while low flying on the lee side of higher terrain in the MacDonnell Ranges. In addition, the ATSB identified a number of factors of increased risk.
Other factors of increased risk included that it was very likely the helicopter was overloaded and beyond the forward centre-of-gravity limit, which would have reduced the helicopter’s power margin and flight control available to the pilot. Secondly, there was moderate turbulence forecast at the time of the accident and the pilot did not check the weather forecast prior to departure. Thirdly, the pilot had an elevated level of alcohol in his system, which was capable of impairing his performance, and increased the likelihood of risk-taking behaviour and mishandling the helicopter in an emergency. Lastly, the helicopter’s emergency locator transmitter was selected ‘OFF’, disabling the automatic crash-activation of an emergency signal.
Safety message
It is important for all pilots to understand that flight planning and prescribed operating limits are safety barriers designed to provide a reasonable margin of safety. Thorough pre-flight planning is essential for avoiding hazardous weather conditions. It is not only important to obtain the relevant weather information to develop a mental picture of the conditions that may be encountered, but also to assess and understand how it relates to the planned flight.
Further, as the helicopter weight and balance has the potential to influence the handling characteristics, it is critical that the loading remains within the prescribed operating limits for the entire flight. Otherwise, as the safety margin steadily erodes, even an experienced pilot may not be able to recover from a rapidly developing unsafe condition.
At low altitude, there is a lower margin for error due to obstacle avoidance. Recognising the risks and hazards of low-level flying, it should be avoided when there is no operational requirement, even if a pilot has been trained and approved to conduct low-level operations. Further information is available from the ATSB publication: Avoidable Accidents No. 1 – Low-level flying.
This accident is also a reminder that blood-alcohol can persist the day after significant alcohol consumption, and the residual effects of alcohol may impair performance, especially in demanding situations.
The occurrence
On the morning of 24 November 2018, the pilot and passenger of a Robinson R22 helicopter, registered VH-KZV, were tasked to assist with the recovery of a motor vehicle near Quartz Hill, located about 63 km east-north-east of Ambalindum Station (departure point), Northern Territory. The pilot was employed by the Ambalindum cattle station for general flying duties, which included cattle mustering and inspecting water bore sites. As such, the pilot was also intending to visit some water bore sites.[1]
At about 0715 Central Standard Time,[2] the pilot refuelled the helicopter with the remaining contents of a fuel drum. A station-hand assisted with preparing the helicopter for departure, which included providing the pilot and passenger with a 20 L drum filled with diesel fuel. The station‑hand reported that this was stored at the passenger’s feet (tail rotor pedals position). He also reported that the weather appeared to be fine for the departure.
At 0732, the pilot’s global positioning system device was powered on while the helicopter was on the concrete helipad in front of the station homestead’s facilities. At 0737, the helicopter departed from the helipad and conducted an air transit to the worker’s accommodation block. The helicopter was on the ground next to the accommodation for 2.5 minutes before it departed from Ambalindum Station. The helicopter flew on a direct track at a height of between 500 and 1,000 ft across relatively open and flat terrain to a bore site, which was located near the boundary of the more rugged terrain of the MacDonnell Ranges.
The pilot and passenger stopped at the bore site[3] for 2 minutes and departed at 0753:50. On departure, the helicopter was levelled off at about 150 ft above ground level, which was below the peaks of the surrounding terrain as it tracked into the MacDonnell Ranges. The last recorded data point was at 0756:30, at which time the helicopter was about 142 ft above ground level with a ground speed of 79 kt. About 56 seconds later (based on the ground speed), the helicopter collided with terrain.
The passenger could not recall any details of the flight, but remembered activating the pilot’s Spot Tracker[4] device after the accident. At 0811, it transmitted its location in SOS mode. A helicopter company in Alice Springs was tasked by the Australian Maritime Safety Authority’s Joint Rescue Coordination Centre (JRCC) to transport a paramedic to the location and attempt a search and rescue (SAR). Ambalindum Station, which was also notified of the activation of the Spot Tracker device, dispatched two employees, the general manager and a station-hand, by road to investigate.
The SAR pilot located the helicopter wreckage at the reported location (Figure 1) and dropped the paramedic nearby to attend to the accident pilot and passenger. The SAR pilot then ferried the two station employees to the accident site. At about 1040, the paramedic found the pilot fatally injured and the passenger seriously injured. The SAR pilot and paramedic, with the assistance of the station employees, retrieved the passenger and transported him to Ambalindum Station for treatment by a retrieval doctor, before moving him to Alice Springs Hospital for further medical attention. The helicopter was destroyed.
The pilot was issued with a Private Pilot Licence (Helicopter) on 10 June 2014 with an endorsement for the Robinson R22 helicopter (R22) under the Civil Aviation Regulations 1988 Part 5 (CAR 5) licencing system. He held a Class 2 aviation medical certificate with an expiration date of 2 February 2020, with the restriction of ‘Reading Correction to be available whilst exercising the privileges of his licence’. His last flight review was completed in February 2018.
On his employment application letter to Ambalindum Station in January 2018, the pilot reported having a total flying experience of 10,000 hours in gyrocopters, 350 hours in the (amateur-built) Cicaré CH-7 helicopter and 800 hours in the R22. At the time of his last medical examination in February 2018, he reported having accrued 800 flying hours. The pilot’s personal diary indicated he had accumulated about 470.5 hours in his current job, which suggested he had about 1,270 hours in the R22.
Validity of qualifications
On 1 September 2014, the Civil Aviation Safety Regulations 1998, Part 61 pilot licencing system was introduced to replace the CAR 5 system. Part 61 included licencing, ratings and endorsements, and provided pilots with a 4‑year period to transfer a CAR 5 licence to a Part 61 licence. In the period 27–29 October 2014, the pilot received low-level and aerial mustering flying training, with an endorsement made by the approved training officer in the pilot’s logbook and on a copy of Appendix II to Civil Aviation Order (CAO) 29.10 (2006): Air service operations – aircraft engaged in aerial stock mustering operations – low flying permission.
On 3 December 2014, the Civil Aviation Safety Authority (CASA) issued the pilot with an approval to conduct aerial stock mustering operations in helicopters under CAO 29.10 subparagraph 6(a). However, subsection 6 of this order was amended on 1 September 2014 by Civil Aviation Order (Flight Crew Licencing) Repeal and Amendment Instrument 2014 (No. 1). The amendment stated that ‘A pilot must not engage in aerial mustering operation unless the pilot is authorised under Part 61 of the Civil Aviation Safety Regulations 1998 to conduct an aerial mustering operation in that kind of aircraft’. Therefore, an approval under CAO 29.10 could no longer be granted. The equivalent authorisation under Part 61 was a low-level rating and mustering endorsement, in accordance with the Part 61 Manual of standards.
During the transition period, the pilot made an application for a Part 61 licence, but with evidence of a mustering endorsement conducted after 1 September 2014 in accordance with CAO 29.10, rather than the Part 61 Manual of standards. Therefore, his Part 61 licence was not issued and he was advised by CASA to resubmit his application with completed forms 61-2I: Notification of issue of CASR Part 61 Operational Rating, and 61-1507: Low-level rating flight test. Completed copies of these forms were required to provide evidence that his CAO 29.10 training complied with the Part 61 Manual of standards requirements for a low-level rating and mustering endorsement. However, CASA did not receive a copy of these forms and never issued the pilot with a Part 61 licence. The pilot was required to hold a Part 61 licence from 1 September 2018 for his licence to be valid.
72-hour history
The pilot’s diary indicated that the accident occurred on his third day of work after 5 days leave. There were no flying hours recorded 2 days prior to the accident, but there was an entry of ‘Chopper going…4 hours’ the day prior to the accident, which suggested this was flight time. There was no indication from his diary or from his colleagues that he was working excessive hours in the week prior to the accident.
The evening prior to the accident, the pilot and station-hands had a ‘few’ alcoholic drinks before and after dinner, and then retired to their private rooms. The evening drinks were reported to be a normal habit and that nothing unusual occurred.
Helicopter information
General description
The helicopter was a two-seat Robinson R22 Beta 2 powered by a Textron Lycoming 4-cylinder O-360-J2A engine. It was manufactured in the United States in January 2010 and registered in Australia in February 2010. It was acquired by the owners on 2 August 2018.
Drive system
The engine has a V-belt sheave bolted directly to its output shaft. V-belts transmit power to the upper sheave, which has an overrunning clutch contained in its hub. The inner shaft of the clutch transmits power forward to the main gearbox, which drives the main rotors, and aft to the tail gearbox, which drives the tail rotors. Flexible couplings are located at the main gearbox input and at each end of the tail rotor drive shaft.
The V-belts are tensioned for flight after engine start by raising the upper sheave. An electric actuator, located between the drive sheaves, raises the upper sheave when the pilot engages the clutch switch. The actuator senses belt tension and automatically switches off when the V-belts are properly tensioned.
Fuel system
The helicopter was fitted with two fuel tanks, a main and an auxiliary, located behind the main rotor mast. Total usable capacity is 100 L (main – 64 L, auxiliary – 36 L). The auxiliary tank is interconnected with the main tank and with its base elevated relative to the base of the main tank, so that the auxiliary will empty first.
Maintenance
The helicopter was issued with its last maintenance release[5] on 12 October 2018, when it completed its last 100-hourly inspection, with 7,000 hours’ time-in-service. Additional work during the 100-hour inspection included replacing the number 1 cylinder, two tail rotor pitch change levers and re-rigging the main rotor flight controls. The maintenance organisation reported that the helicopter had completed four 100-hourly inspections since the last 2,200-hour major overhaul. The organisation’s licenced aircraft maintenance engineer (LAME) had completed the last two of those four inspections (since it was acquired by the new owners) and indicated that the helicopter was overall in good condition.
On 23 November 2018, the day before the accident, the LAME[6] went to Quartz Hill to replace the electric actuator fitted to the helicopter. The actuator and V-belts were replaced, followed by a cooling fan balance. No maintenance release was provided to record the work, but the pilot reported to the LAME that the helicopter had accumulated about 15 hours since the last 100‑hourly inspection. The LAME returned to Alice Springs with the understanding that the pilot would phone that evening with the actual hours but did not hear from him.
Meteorological information
When transporting the passenger from the accident site to Ambalindum Station, the SAR pilot asked him what happened. Neither the SAR pilot nor the paramedic were certain of the passenger’s reply and the passenger had no recollection of the conversation. However, the paramedic recalled words to the effect that the ‘wind lifted them up’, that the pilot had said to him (passenger) ‘look at this [expletive]’, ‘and we were lifted up in the air’. The SAR pilot recalled the passenger indicated that the accident pilot had told him they ‘better pull-up to get a bit more height/air to make it safer’.
Planning
The station homestead had a local Wi-Fi network, so that the workforce could use their personal electronic devices, and computers located in the office area. The general manager for the company, who was at the station at the time, reported that the office computers were for management staff and not a common access area. The pilot would have been granted access to use them for flight planning purposes, but he had not requested access and the manager was not aware of him ever using them. The ATSB reviewed the pilot’s iPad and iPhone. A review of applications and browsing history on the iPad and iPhone found no evidence that either was used to access any aviation-related applications or aviation-related services (such as the Bureau of Meteorology) on either the day of, or day prior, to the accident. However, both were in use in the week of the accident.
Weather forecast
The Bureau of Meteorology graphical area forecasts valid between 0230 and 1430 on 24 November included moderate turbulence below 7,000 ft above mean sea level throughout the area. The aerodrome forecast for Alice Springs Airport[7] (about 125 km east-north-east of the accident site), issued at 0249 and valid from 0330 24 November to 0330 25 November, reported CAVOK[8] conditions, but with a wind of 18 kt, gusting to 28 kt, from 320°. In addition, the remarks included moderate turbulence below 5,000 ft above mean sea level from 0630.
Reported weather conditions
On 24 November, the recorded aerodrome weather report for Alice Springs Airport between 0600 and 0730 indicated a wind direction of 330–340° at about 15 kt. However, at 0758, SPECI[9] conditions were recorded with a wind speed of 18 kt, gusting to 29 kt. The Arltunga weather station, located about 40 km east of the accident site, recorded a wind speed of 14 kt[10] from a direction of 360°, QNH 1015 hPa[11] and a temperature of 30 °C, at 0800.[12] The Ambalindum Station personnel interviewed by the ATSB reported that the weather was fine and clear in the morning at the station.
The SAR pilot reported that engine start in his Bell 206 at Alice Springs Airport was at 0940. He reported that the weather was turbulent all the way out to the accident site, and estimated it was moderate to severe in the ranges with a wind speed of 20 kt, gusting to 40 kt. He reported that, on arrival at the accident site he encountered a strong downdraft at about 100 ft above ground level.
The SAR pilot also stated that he took three approaches to land due to the turbulence at the accident site with the paramedic but could not remember what occurred when he subsequently ferried the station‑hand and general manager into the site. The paramedic recalled only one approach to land, but the station-hand recalled they took three approaches to land, that the helicopter was being thrown around and that the SAR pilot had warned him about downdrafts. The general manager recalled they took one approach but was aware that the pilot was concerned about the flying conditions.
The station-hand recalled that, while on the ground at the accident site, he felt the wind tunnelling down the ravine. He reported that it was cycling from ‘nothing, to heavy wind to slight breeze, then nothing’. In consideration of the weather forecast and reports, the ATSB requested analysis from the Bureau of Meteorology for the likelihood of mountain or lee wave activity in the area at the time of the accident.
Bureau of Meteorology analysis
The Bureau of Meteorology reported the following:
The mean sea level pressure chart for the morning of the accident showed a deep trough and low-pressure system moving into the central and southern parts of the Northern Territory from Western Australia. Conditions ahead of the trough saw moderate to fresh north-east to north-west winds. The synoptic pattern was conducive to moderate turbulence, and, particularly after sunrise, gusty and turbulent flow was anticipated as the stronger winds from aloft mixed to the surface.
At the ridge-top level of the ranges north of Alice Springs, approximately 2,000 ft to 4,000 ft above mean sea level, the winds observed at 0830 on 24 November were 25 kt. The strong north to north-west winds, being perpendicular to the ranges, were conducive to mechanical turbulence, especially in the lee of the ranges. The height of the ridge being over 1,000 ft, and the strength of the winds perpendicular to the ridge being over 25 kt, indicated the necessary requirements for the occurrence of mountain waves.
The aerological diagram showed the wind strength increasing with height above the height of the ridge, as well as instability in the atmosphere above ridge-top level. However, no evidence was found for mountain waves in the cloud patterns observed on the satellite imagery. Therefore, the occurrence of mountain waves remained inconclusive.
The breaking of an inversion layer can also be associated with moderate turbulence. The onset of gusty conditions at Alice Springs Airport at 0758 indicated the overnight inversion would have broken by then, with stronger winds aloft mixing down. Broadscale moderate turbulence was especially likely at that time.
Terrain-induced turbulence
According to the United States Federal Aviation Administration (2016) Pilot’s handbook of aeronautical knowledge, ground topography can break up the flow of the wind and create wind gusts that change rapidly in direction and speed. While the wind may flow smoothly up the windward side of higher terrain, on the leeward side it attempts to follow the contour of the terrain and is increasingly turbulent. The stronger the wind, the greater the downward pressure and turbulence. The downdrafts can be severe in valleys due to the effect of the terrain. Hence, it is recommended to avoid flying in this area when strong winds are present or likely to occur. Figure 2 depicts the potential wind conditions on the lee (right) side of terrain.
Figure 2: Potential wind conditions on the lee side of terrain
Source: Federal Aviation Administration (2012)
Recorded information
The ATSB examined the pilot’s iPad, iPhone, GoPro camera and GPS devices. There was no evidence that the iPhone was in use at the time of the accident and no location data was available to create a flight path.[13]
Global positioning system data
Data was recovered from the pilot’s GPS device. The flight profile on the day before the accident (23 November) revealed the pilot had been flying back-and-forth along a dry riverbed at low‑level (below 200 ft) near Quartz Hill. The helicopter then tracked back‑and‑forth between Quartz Hill and Ambalindum Station. The last sector recorded an arrival time at Ambalindum Station helipad of 1815.
For the accident flight, the first recorded data point was from the helipad at 0732 (Figure 3).[14] After transiting to the workers’ accommodation block, the helicopter departed at 0740 for the bore site.
Figure 3: Departure from the homestead
Source: Google earth, annotated by the ATSB
Figure 4 shows that, about 2 minutes after taking off from the bore site, at 0755:46, the helicopter was levelled off at about 150 ft above ground level and then entered the MacDonnell Ranges. The final data point, recorded at 0756:30, was located at a height of about 142 ft, with a ground speed of 79 kt,[15] on a direct track towards the accident site. Based on this ground speed, the ATSB estimated that the time between the last data point and the accident site was 56 seconds.
Figure 4: GPS track from the bore site to the accident site
Source: Google earth, annotated by the ATSB
GoPro data
The GoPro camera did not hold a recording of the accident flight. However, a total of 69 videos and 25 images were recovered, dated from 1 January 2012 to 15 June 2016. The time and date of the GoPro can be set manually or by Wi-Fi. It could not be determined if the recorded dates were correct, but the files included videos of the accident pilot flying an R22 from a different operator. It was therefore likely that the files were from his previous employment.
The video files showed the pilot engaged in low flying and cattle mustering activities throughout the time period. They included low-level contour flying between mustering tasks, along a river and along a dry riverbed (see Figure 5 example). Mustering videos included manoeuvring the R22 at up to 50° angle of bank with indeterminable pitch changes, coupled with skidding or side-slipping[16] within about 1–2 rotor diameters of the ground.
Figure 5: Example of low flying in previous employment
Source: ATSB
Wreckage and impact information
Accident site
The accident site was in the MacDonnell Ranges at an elevation of about 1,850 ft, 31 km east of Ambalindum Station. The helicopter impacted the ground on a downslope, in an easterly direction, and continued down the slope. It then came to rest on the far side of the riverbed in a southerly direction, with the left side resting against the upslope of the far bank.
The ATSB noted there was higher terrain, orientated east-west, immediately to the north of the initial point of impact. This was the reported direction for the prevailing wind at the time of the accident.
Impact sequence
The impact sequence started with the main rotor severing the upper branches of a small tree, indicating 10–15° right bank, before the tail stinger struck a rock and was separated from the tailcone. A tail rotor blade then separated after impacting a tree branch at about the same time as the right skid contacted the ground adjacent to protruding rocks (Figure 6), which were struck by the underside of the helicopter. About half way down the slope the helicopter passed through a tree, which fragmented the cabin plexiglass and removed the front landing skid cross-tube.
Just prior to crossing the riverbed, the main rotor disc struck and separated the tail rotor driveshaft and empennage from the airframe. The empennage was located just prior to crossing the riverbed, to the right of the accident path. The driveshaft was found on the far side of the riverbed to the right of the accident path and beyond the main wreckage.
Figure 6: Impact sequence
Source: Alice Springs Helicopters, annotated by the ATSB
Wreckage examination
The helicopter’s clock had stopped at about 0756 and the engine hour-meter indicated 6,893.36 hours. The helicopter was fitted with an impact activated emergency locator transmitter (ELT), which was found selected to the ‘OFF’ position.[17] In addition to the pilot and passenger, the helicopter was loaded with:
a double-barrelled shotgun and bolt action rifle with ammunition
two six-packs of beer (no evidence that any were consumed)
empty 20 L drum (perforated, but strong diesel fuel odour)
empty 10 L water container (used for testing water flow rate at bore sites)
bore test equipment (data logger)
two webbing straps and a bag of lifting equipment
between one-third and two-thirds fuel contents in the main fuel tank and unusable fuel in the auxiliary fuel tank.[18]
The ATSB found no pre-existing defects with the rotors, drivetrain or flight controls, which would have prevented normal operation. The tail rotor driveshaft was folded by the main rotor strike. It was also noted to have been pulled apart at the intermediate and aft flex couplings (Figure 7). This indicated a loss of energy from the main rotor system occurred at some time prior to the main rotor striking the tailcone.[19] A fuel test on-site and at the point of departure did not identify any visual contaminates or water.
Figure 7: Tail rotor driveshaft
Source: ATSB
The engine and a majority of the airframe was retrieved from the accident site and transported to Alice Springs Airport where further inspections of the drivetrain and engine components were performed. No pre-existing defects were found to prevent normal operation. The engine was then removed from the wreckage and transported to Brisbane for further examination under the supervision of the ATSB.
Engine tests and inspections
On 8 and 9 January 2019, tests and inspections were conducted on the recovered engine. No fault was identified that would have prevented normal operation of the engine. Damage to the engine-cooling fan and the presence of dirt inside the number 2 cylinder indicated the engine was operating at the time of initial impact.
The V-belts were found intact and scoring damage to the V-belt actuator was identified. Robinson advised the ATSB that the length of the actuator indicated it was extended in the normal position for flight and that the scoring was consistent with the upper sheave rotating on contact with the actuator as the helicopter’s structure distorted on impact (Figure 8). This indicated that the engine was driving the V-belts and upper sheave at impact.
Figure 8: Scoring to the clutch actuator
Source: ATSB
The lower third section of the engine-cooling fan exhibited ‘gathering’ of metal in the direction of fan rotation. This suggested that the engine was producing power at the time of impact. The exhaust was crushed and the carburettor throttle arm bent, resulting in the throttle butterfly valve being forced towards the full closed position. It was concluded that the damage to the engine components likely resulted in engine stoppage shortly after the initial ground impact.
Medical and pathological information
A post-mortem examination was conducted on the pilot at Royal Darwin Hospital. The forensic pathologist concluded that the pilot received multiple injuries, sustained during the impact sequence, which resulted in his fatality. A sample of bloodstained chest cavity fluid and urine contents were submitted for toxicological analysis.
The pilot’s toxicology results included 0.20 per cent alcohol detected in the bloodstained chest cavity fluid and 0.14 per cent alcohol detected in the urine. The forensic pathologist confirmed that the bladder was intact, but that fermentation with microbiologically generated alcohol might be an issue as decomposition had started.[20] Therefore, he advised seeking assistance from a subject matter expert for interpretation of the alcohol results. The ATSB consulted with the forensic scientist who conducted the toxicology, and engaged a forensic and aviation pathology consultant.
The forensic scientist reported that during their routine screen of the chest cavity fluid, they noted the presence of a number of compounds that are typically indicative of decomposition. She reported that alcohol can be produced during decomposition, ‘however the high alcohol levels observed for this case (especially in the urine, which is typically less prone to post-mortem alcohol production) don’t appear to suggest extensive post-mortem production of alcohol’.
The consultant reviewed the material, including the correspondence with the forensic pathologist and forensic scientist, and provided an interpretation for the alcohol results. She reported that, for the bloodstained chest cavity fluid, ‘the possibility that some of this level is not the result of ethanol [alcohol] ingestion prior to death but the result of decomposition changes in the blood occurring after death, exists. It is however, still a significant level… Urine is less susceptible to the effects of decomposition than blood and chest fluid, particularly in the absence of injury [intact bladder] suggesting that the finding is a significant indicator of ingested alcohol’.
According to the consultant, blood alcohol levels greater than 0.05 per cent have the effect of lowering caution, worsening of judgement and reasoning. Higher levels of around 0.1 per cent may affect these more and impair coordination and reaction time. Blood alcohol levels generally decrease at a rate of 0.01 per cent per hour. If the pilot was drinking heavily the evening prior to the accident flight, his blood alcohol level could still have been elevated during the flight such as to affect his piloting performance. It is possible that heavy drinkers may develop some tolerance to the effects of alcohol.
The consultant concluded that the time required to retrieve the pilot resulted in sub‑optimal collection of specimens on which to perform the analysis. Both samples showed the presence of considerable amounts of alcohol, but the precise level of blood alcohol could not be ascertained. However, given the measured levels and degree of decomposition [early stages], ‘it is highly likely that alcohol was present in blood at a level capable of impairing pilot performance’.
Survival aspects
The accident occurred at about 0757 at a remote location. The main rotor tree strike, and ground impact marks, suggested the initial impact was in a relatively level attitude and survivable. However, about half way downslope, the helicopter passed through a tree, resulting in the fragmentation of the plexiglass and separation of the landing skid front cross‑tube from the airframe, which compromised the liveable space of the cabin. This exposed the pilot and passenger to multiple injuries as the helicopter continued on its trajectory over rocky terrain and across a dry riverbed, before coming to rest upslope on the far side.
The pilot and passenger seats were both fitted with lap and shoulder restraints (three-point lap‑sash seatbelts). The seat harnesses were found in various conditions. The pilot’s shoulder harness was cut away by first responders and his lap belt was found unbuckled. The passenger’s lap strap had completely pulled through its clasp, leaving the clasp inside the buckle without a strap attached. The occupants were not wearing helmets and both were found with head injuries.
Emergency locator transmitter
The helicopter was fitted with an ELT in the transmission bay area, above the horizontal firewall. The ELT had a protected 3-position toggle switch. The three selections were OFF, ARM and ON. The ELT was found by the ATSB to be in the OFF position. Therefore, it could only be activated by an individual accessing the device and selecting it to the ON position. The passenger reported that he was intermittently conscious following the accident and that the pilot did not regain consciousness.
In the ARM position, the ELT will automatically activate if the deceleration is sufficient in magnitude and direction. The examination of the accident site did not indicate that the helicopter was subject to either a high vertical or horizontal deceleration. In 2013, the ATSB published a review of the effectiveness of ELTs in aviation accidents, and found that even in a high deceleration impact they only activated 40–60 per cent of the time in the ARM mode.
Search and rescue sequence
Ambalindum Station staff were provided with a Spot Tracker device. The Spot Tracker is a personal tracking device, which sends a GPS location signal at a set time interval. In addition to the routine signal, the device has a button for an SOS signal to provide an alert for emergency assistance. The pilot was carrying his device on the flight, but the passenger was not. The passenger could not recall why he did not have his device. However, at about 0811, the passenger was able to activate the pilot’s Spot Tracker in SOS mode.
The Spot Tracker service contacted the station owners and the JRCC. The SAR pilot was contacted by the station owners and then by the JRCC who also activated the paramedic. The paramedic met the SAR pilot at their Alice Springs Airport hangar.
The SAR pilot achieved engine start at 0940, and the paramedic arrived at the scene of the accident at about 1040, while the SAR pilot was ferrying the station personnel to the site.
The station-hand and general manager were left at the site while the pilot ferried the paramedic and passenger to Ambalindum Station, where a trauma doctor was waiting. Weather storm cells started to develop after arrival at Ambalindum Station and at 1350, the SAR pilot ferried the trauma doctor with the passenger to Alice Springs. His triage at Alice Springs Hospital was recorded as occurring at 1500.
Helicopter performance
The ATSB used the Arltunga weather station to calculate the accident site pressure altitude and density altitude, which were 1,796 ft and 4,000 ft respectively. According to the R22 Pilot’s operating handbook (POH), the helicopter was capable of producing at least maximum continuous power, and likely take-off power, under these conditions.
Weight and balance
The published maximum all-up-weight limit for the R22 was 622 kg.[21] However, there was no record of how much fuel was on board at departure and the fuel contents at the accident site was based on visual estimates. Therefore, the ATSB calculated the weight and balance progressively from full main tank contents to empty main tank contents. The calculations included the pilot and passenger’s weights, 20 L of diesel fuel at the passenger’s tail rotor pedals position, and 20 kg for the additional articles.
The results provided in Table 1 indicated that at full main tank fuel, the helicopter’s operating weight was above the limit for maximum all-up-weight, and the centre-of-gravity (‘Arm’) was beyond the forward limit. At the reduced fuel load of 1/3–2/3 main tank fuel observed at the accident site, the helicopter’s operating weight was still above the maximum all-up-weight and the centre-of-gravity was further forward of the forward limit.
A negative weight margin indicates a higher weight than the maximum all-up-weight, and a negative arm indicates a centre-of-gravity position forward of the forward limit. The range of the centre-of-gravity was 160 mm from the aft limit to the forward limit.
Table 1: Weight and balance
Main tank contents
All-up-weight (kg)
Weight margin (kg)
Arm (mm)
Full
659
-37
-37.7
Two-thirds
643
-21
-46.2
One-third
626
-4
-48.2
Empty
613
9
-55.9
The high all-up-weight of the helicopter would result in a high power requirement under normal flight conditions. This would have reduced the power margin available for contingency situations, such as an emergency climb. As stated in the United States Federal Aviation Administration (2012) Helicopter flying handbook ‘Excessive weight reduces the flight performance in almost every respect’.
Robinson had published a caution in the R22 POH for loading the helicopter near the forward centre-of-gravity limit, as follows:
CAUTION: Fuel burn causes the CG [centre-of-gravity] to move forward during flight. Always determine safe loading with empty fuel as well as with takeoff fuel. Payload may be limited by forward CG as fuel is burned.
The caution provided by Robinson was consistent with the advice published by the United States Federal Aviation Administration in their Helicopter flying handbook, which provided the following information for a centre-of-gravity forward of the forward limit:
A forward CG may occur when a heavy pilot and passenger take off without baggage or proper ballast located aft of the rotor mast. This situation becomes worse if the fuel tanks are located aft of the rotor mast because as fuel burns the CG continues to shift forward.
The handbook further indicated that the position of the centre of gravity will influence the handling characteristics of the helicopter. The fuselage acts as a pendulum suspended from the rotor, and when the centre of gravity is directly under the rotor mast, the fuselage should remain horizontal. If the centre of gravity is beyond the forward limit, the nose of the helicopter will tilt down. Consequently, a pilot would have to apply aft cyclic control to raise the nose and balance the helicopter. However, as fuel is consumed and the centre of gravity continues to move forward, a pilot could rapidly lose rearward cyclic control. In this condition:
A pilot may also find it impossible to decelerate sufficiently to bring the helicopter to a stop. In the event of engine failure and the resulting autorotation, there may not be enough cyclic control to flare properly for the landing.
The GPS data indicated the pilot flew the approach and departure to the bore site, just prior to the accident, in a northerly direction, which was into wind. In a headwind, the forward centre-of-gravity may be less noticeable to the pilot as the cyclic is displaced forward of the nil wind position, thereby providing a greater aft cyclic range than in a nil wind or tail wind condition.
Strong winds and turbulence
Robinson has published a safety notice (SN-32) in the R22 POH on the subject of flight in strong winds or turbulence.[22] The safety notice included the following information:
Flying in high winds and turbulence should be avoided. If turbulence is encountered, the following procedures are recommended:
1. Reduce power and use a slower than normal cruise speed. Mast bumping is less likely at lower airspeeds.
2. For significant turbulence, reduce airspeed to 60–70 knots.
3. Tighten seat belt and rest right forearm on right leg to minimize unintentional control inputs. Some pilots may choose to apply a small amount of cyclic friction to further minimize unintentional inputs.
4. Do not overcontrol. Allow aircraft to go with the turbulence, then restore level flight with smooth, gentle control inputs. Momentary airspeed, heading, altitude, and RPM excursions are to be expected.
5. Avoid flying on the downwind side of hills, ridges, or tall buildings where turbulence will likely be most severe.
Employment of the pilot
In early 2018, the pilot was employed by Hewitt Cattle Australia, the owners of Ambalindum Station and the accident helicopter, in accordance with their recruitment process. This included the pilot’s submission of a résumé with referee details and relevant aviation qualification documents. The documents included a copy of his CAR 5 private pilot licence, dated 10 June 2014, and a copy of his CAO 29.10 Appendix II and log book endorsements for low flying and mustering training, dated 29 October 2015. It was agreed that the pilot’s completion of a flight review would satisfy the employer’s requirements.
The pilot’s application was vetted by his prospective employer and their insurance company. This included a check of his log book to verify he had completed the flight review as agreed. Although the pilot did not hold a commercial licence, CASA confirmed that aerial mustering may be conducted as a private operation over land occupied by the owner of the aircraft with the appropriate licence, rating and endorsement.
At the time, the pilot submitted his documents to his prospective employer, his CAR 5 licence was still valid and there was about 7 months remaining until the end of the transition period to the Part 61 licence. It was considered unlikely that the discrepancy associated with his low flying and mustering training would have been identified by anyone who did not have an intimate knowledge of the Part 61 licencing system.
While flying in the MacDonnell Ranges, Northern Territory, VH-KZV collided with terrain on a downslope. The pilot was fatally injured and the passenger received serious injuries. The helicopter was substantially damaged. The time of the accident was within a period of a weather forecast for moderate turbulence in the area.
The on-site wreckage examination and additional testing of the engine found no evidence of a pre‑existing defect to prevent normal operation of the helicopter. Therefore, it was almost certain that the engine was operating and driving the rotors at initial impact.
This analysis will discuss the pilot’s flight planning and loading of the helicopter, the likelihood that his performance was impaired by alcohol, and the operational state of the helicopter’s emergency locator transmitter (ELT).
Collision with terrain
The pilot’s global positioning system device track data, recovered from the accident site, indicated the helicopter levelled-off at about 150 ft above ground level on entry to the MacDonnell Ranges. This flight profile was maintained to the last recorded data point (less than 1 minute before the accident) at which stage the helicopter was about 142 ft above terrain. On review of the track data for the previous day, and GoPro camera footage of previous work experience, the pilot appeared to have a habit of manoeuvring his helicopter to contour fly along dry riverbeds. The helicopter’s track from the bore site was towards rugged terrain with dry riverbeds and not a direct track towards their destination of Quartz Hill. Therefore, it was very likely the pilot was operating the helicopter at low-level and possibly engaged in contour flying, just prior to the accident.
The meteorological conditions at the time of departure were reported as fine, but moderate turbulence was forecast for the period of the accident flight. The final track of the helicopter placed its path on the lee side of higher ground for the prevailing winds. At about that time there was a change in weather conditions recorded at Alice Springs Airport, indicating stronger winds aloft were mixing with the surface winds. The Bureau of Meteorology’s analysis indicated that these winds could have generated at least moderate mechanical turbulence, with the potential for strong downdrafts in the lee of higher terrain. This was consistent with what was experienced by the search and rescue pilot on arrival at the scene of the accident site and suggestive of the comments made by the passenger during his retrieval.
In consideration of the track data, meteorological conditions, accident site and wreckage, it was likely the helicopter encountered a downdraft when low flying in the MacDonnell Ranges with insufficient height to recover, resulting in the collision with terrain.
Flight planning
Ambalindum Station was equipped with an office and computers that had internet access. However, the employer’s general manager reported that the pilot did not use, or request to use, the office computers for flight planning. Further, the ATSB found no evidence on either the pilot’s iPad or iPhone to indicate he had accessed any flight planning data in preparation for the accident flight.
Consequently, the pilot was most likely unaware of the forecast conditions of moderate turbulence and strong winds for his area of operation. Prior knowledge of potentially hazardous meteorological conditions at low-level may have resulted in him selecting an alternate flight path and/or higher altitude to mitigate the associated risks.
Helicopter performance
ATSB calculations of the loading of the helicopter indicated it was likely overweight, with a centre‑of-gravity beyond the forward limit, for the entire accident flight. However, the performance charts in the pilot’s operating handbook did not provide results beyond the published limits, and therefore, the performance of the helicopter under the actual conditions could not be determined.
The engine was capable of producing sufficient power for normal flight in the overloaded condition, which was evidenced by the fact that the helicopter had taken off and had been flying for about 20 minutes. However, a downdraft would increase the power required if the pilot attempted to recover lost height during an uncommanded descent. In this situation, the power required by the rotors could rapidly exceed the power available from the engine, resulting in a loss of power margin and a forced descent.
The location of the fuel tanks, behind the main rotor mast, meant that the centre-of-gravity would move forward in-flight as fuel was consumed. This would reduce the range of aft cyclic movement available to the pilot, used to flare and decelerate the helicopter. The into-wind approach and departure, flown to the bore site just prior to the accident, likely increased the available aft cyclic range compared with a nil wind or tail wind condition. Therefore, the pilot may not have been aware of the reduction in aft cyclic control that had already occurred.
After departure from the bore site, the helicopter’s track towards the accident site resulted in a wind direction from the left rear quarter (left of the nose between 90–130°). Any rearward component of wind, combined with a reduction of aft cyclic control, would have severely compromised the ability of the pilot to reduce the forward speed of the helicopter.
It was possible that the downdraft would have exceeded the capability of the helicopter loaded within the prescribed limits. However, without knowledge of the actual direction and strength of the downdraft encountered, it could not be determined if the overloaded condition and forward centre‑of-gravity contributed to the collision with terrain. Despite this, if hazardous weather was encountered at low-level, the combination of a reduced power margin and aft cyclic control would reduce the response available, thereby increasing the risk of a collision with terrain.
Impaired pilot performance
Research conducted for the ATSB (Newman, 2004) into alcohol and human performance highlighted that:
In simple terms, alcohol impairs human performance…
It has detrimental effects on cognitive functions and psychomotor abilities. Risk taking behaviour may result, and a full appreciation of the consequences of a planned action may not be possible… Adverse effects can also persist the day after alcohol ingestion, with reductions in alertness, concentration and vestibule-ocular function, and increases in anxiety all being reported…
Alcohol has been shown to impair registration, recall, and organisation of information, leading to increased reaction times and/or a greater number of errors…
…performance has also been found to suffer most when an unexpected or unanticipated event occurs.
The pilot’s toxicology report results indicated an elevated level of alcohol in his urine. The toxicologist, and forensic and aviation pathology consultant, concluded that the level of alcohol present was unlikely to be solely the result of decomposition. The consultant also indicated that it was highly likely there was sufficient alcohol present in his blood at a level capable of impairing his performance and that an elevated level of alcohol has the effect of lowering caution, worsening judgement and impairing coordination and reaction time, although heavy drinkers may develop some tolerance to these effects.
The ATSB noted that the evidence of previous low flying suggested his actions may have been normal behaviour and not influenced by alcohol. Therefore, it could not be concluded that his elevated level of alcohol contributed to the accident but considered that it increased the likelihood of risk-taking behaviour and mishandling the helicopter in an emergency.
Emergency locator transmitter
Emergency locator transmitters are radio beacons carried on most aircraft so that in the event of an accident in a remote location, the aircraft wreckage and its occupants can be located quickly by search and rescue (SAR) operations. Finding the aircraft wreckage quickly not only increases the chance of survival of the occupants, but also reduces the risk to pilots of SAR aircraft who commonly need to operate in marginal weather conditions and over mountainous terrain (ATSB 2013).
The inspection of the wreckage found that the emergency locator transmitter (ELT) was selected OFF, rather than ARM. The ARM mode would provide an impact-activated signal. The ELT was located in the transmission area and while selected OFF, it required an individual to access it and select the ON mode for it to transmit a signal. However, the pilot did not regain consciousness following the accident and therefore the ELT was never activated. If not for the pilot’s Spot Tracker device, it was possible that the search and rescue response may not have commenced for some time after the accident, delaying medical treatment for the passenger.
ATSB research into the effectiveness of ELTs in aviation accidents (ATSB, 2013) established that they functioned as intended in about 40-60 per cent of accidents in which their activation was expected. In the accidents where it did not work effectively or at all, the ATSB found that this was due to the ELT not being armed before flight, incorrect installation or flat batteries, a lack of water or fire protection, damage to the ELT during the impact sequence, or the way in which the aircraft came to rest after the impact. Activation of the ELT in the ARM mode requires a high deceleration. Examination of the accident site and wreckage suggested it was possible that the ELT would not have activated in the ARM mode, but this could not be verified. Therefore, it could not be concluded that the OFF-mode selection of the ELT would have hindered a response to the accident, but not having it selected to ARM was considered to increase the risk of a delayed response.
Findings
From the evidence available, the following findings are made with respect to the collision with terrain involving a Robinson R22, registered VH-KZV, 125 km east-north-east of Alice Springs Airport, Northern Territory, on 24 November 2018. These findings should not be read as apportioning blame or liability to any particular organisation or individual.
Contributing factors
It was very likely that the pilot was operating the helicopter at low-level when it encountered a downdraft with insufficient height to recover, resulting in a collision with terrain.
Other factors that increased risk
The pilot did not consult any weather forecast data before departure, which increased the risk of him selecting a flight path through the MacDonnell Ranges that was not appropriate for the forecast wind conditions and turbulence.
It was very likely that the helicopter was overweight on departure and the centre-of-gravity was beyond the forward limit for the entire flight, which increased the risk of the pilot experiencing reduced control authority over the helicopter.
It was very likely the pilot's blood alcohol content was capable of impairing his performance, which increased the likelihood of risk-taking behaviour and mishandling the helicopter in an emergency.
The impact-activated emergency locator transmitter fitted to the helicopter was selected off, which increased the risk of a delayed emergency response.
Other findings
There was no fault found with the helicopter to prevent normal operation. It was almost certain the engine was operating and driving the rotors when it collided with terrain.
The pilot’s Private Pilot Licence (Helicopter), and low-level and aerial mustering qualifications had not been transferred to the Civil Aviation Safety Authority’s new licencing system and therefore, were not valid at the time of the accident.
General details
Pilot details
Licence details:
Private Pilot Licence – Helicopter (invalid from 1 September 2018)
Endorsements:
R22 (invalid from 1 September 2018)
Ratings:
Nil
Medical certificate:
Class 2, valid to 2 February 2020
Aeronautical experience:
Approximately 1,270 hours in the R22
Last flight review:
February 2018
Proactive safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence:
Operator safety management improvements
Subsequent to the accident, Hewitt Cattle Australia (HCA) elected to contract out the majority of its aviation operations to Air Operator Certificate holders, including all rotary operations.
Through their recently appointed a work health and safety manager, they commenced a review of their aviation safety system. A third party aviation expert consultant was engaged to lead the review. As a result of that review, HCA developed further improvements to their aviation safety system in order to enhance the safety standards, which included the development of:
An aviation safety management system, which borrows elements contained in Civil Aviation Advisory Publication SMS-01 v1.1: Safety management systems for regular public transport operations.
An aviation safety management manual, which is based on the recommended framework contained in the International Civil Aviation Organization’s safety management manual, and incorporates best practice from the Flight Safety Foundation basic aviation risk standard, and the International Association of Oil and Gas Producers aircraft management guidelines. The manual has been tailored for HCA’s operations, with a specific focus on the areas of safety policy, risk management procedures, hazard and occurrence reporting, ‘just culture’, and assurance, specifically focused on the audit of service providers and suppliers.
A revised safe operating procedure for pilots, which is integrated with the HCA safety management system (in which pilots operating HCA aircraft have been inducted). This includes a number of additional requirements designed to decrease the likelihood of similar accidents in the future, including: pilot minimum experience requirements based on industry best practice; the basic aviation risk standard pilot runway and helicopter landing site assessment process; a process for the conduct of an abbreviated risk assessment by pilots; safety occurrence reporting requirements; Civil Aviation Safety Authority drug and alcohol training for pilots (which pilots operating HCA aircraft have undertaken); adverse weather policy; approved and prohibited flying activities; and restriction on carriage of passengers.
The aviation safety management manual creates a framework to allow for open reporting of safety occurrences based on the ‘just culture’ philosophy. This is aimed at shaping the behaviour and the culture of pilots to ensure that activities, which are not in line with HCA’s expectations, are less likely to occur. HCA considers that this cultural shift is important as the remote and expansive location of its aviation operations affect management’s ability to constantly view and assess a pilot’s general and specific flight conduct. The manual also provides a process for monitoring and auditing the currency of pilot training, ratings and endorsements on HCA’s training management system.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Alice Springs Helicopters
Bureau of Meteorology
Civil Aviation Safety Authority
Forensic and aviation pathology consultant
Forensic Science South Australia
Hewitt Cattle Australia employees
Northern Territory Police
Robinson Helicopter Company
Royal Darwin Hospital
St John Ambulance – Northern Territory.
References
Australian Transport Safety Bureau 2019, AO-2016-156: In-flight break-up involving Robinson R44, VH-ZNZ, 41 km NW Mossman, Queensland, on 18 November 2016, ATSB, Canberra.
Australian Transport Safety Bureau 2013, AR-2012-128: A review of the effectiveness of emergency locator transmitters in aviation accidents, ATSB, Canberra.
Federal Aviation Administration 2016, Pilot’s handbook of aeronautical knowledge, chapter 12: weather theory (FAA-H-8083-25B), US Department of Transportation, Oklahoma City United States.
Federal Aviation Administration 2012, Helicopter flying handbook (FAA-H-8083-21A), US Department of Transportation, Oklahoma City United States.
Wagtendonk WJ 2011, Principles of helicopter flight, 2nd edn, Aviation Supplies & Academies, Inc. Washington United States.
Submissions
Under Part 4, Division 2 (Investigation Reports), Section 26 of the Transport Safety Investigation Act 2003 (the Act), the Australian Transport Safety Bureau (ATSB) may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. Section 26 (1) (a) of the Act allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to Alice Springs Helicopters, Bureau of Meteorology, Civil Aviation Safety Authority, the forensic and aviation pathology consultant, Forensic Science South Australia, Hewitt Cattle Australia, Northern Territory Police, Robinson Helicopter Company, Royal Darwin Hospital, St John Ambulance Northern Territory and the United States National Transportation Safety Board.
Submissions were received from Hewitt Cattle Australia, the Civil Aviation Safety Authority, and Forensic Science South Australia. The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Preliminary report
Report release date: 30/01/2019
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
What happened
On 24 November 2018, at about 0800 Central Standard Time,[1] a Robinson R22 helicopter, registered VH-KZV, collided with terrain about 125 km east-north-east of Alice Springs Airport. The pilot was fatally injured and the passenger was seriously injured. The helicopter was substantially damaged.
The pilot held a private helicopter pilot licence and was employed by a cattle station for general flying duties, which included cattle mustering. On the morning of the accident, the pilot and passenger were tasked to assist with the recovery of a motor vehicle, located about 63 km east-north-east of Ambalindum Station (departure point). A station hand assisted them with preparing the helicopter for departure. The station hand could not recall the actual time of departure, but estimated it was between 0730 and 0745.
At about 0811, the pilot’s Spot Tracker device transmitted its location in SOS mode.[2] A local helicopter company in Alice Springs was subsequently tasked by the Joint Rescue Coordination Centre to transport a paramedic to the reported location and conduct a search and rescue. In addition, Ambalindum Station dispatched two employees by road to investigate. The search helicopter pilot located the wreckage of the R22 at the reported location, and the paramedic subsequently attended to the accident pilot and passenger. At about 1045 the paramedic found the pilot deceased and the passenger in a serious condition. The rescue helicopter departed to collect the two station employees who were enroute to assist with the emergency response. The rescue helicopter pilot and the paramedic, with the assistance of the two station employees, retrieved the passenger and transported him to Ambalindum Station for treatment by a retrieval doctor, before transporting him to Alice Springs Hospital for further medical attention.
Figure 1: Robinson R22 helicopter, VH-KZV, main wreckage site
Source: ATSB
The ATSB attended the accident site on 26 and 27 November 2018. The helicopter’s clock had stopped at about 0756. The helicopter had impacted the ground on a downslope, in an easterly direction, and continued down the slope, producing debris as it struck rocks and trees, before crossing a dry creek bed. The helicopter came to rest on the far side of the creek bed, in a southerly direction, with the port side of the helicopter resting against the upslope of the far bank. The main rotor disc struck and separated the rear section of tailcone as a consequence of the accident sequence. Significant torsional deflection of the tail rotor driveshaft intermediate flexible coupling indicated that it was rotating when the strike occurred.
The ATSB found no pre-existing defect with the rotors, transmission, sprag clutch, drive belts or flight controls, which would have prevented normal operation. The main fuel tank had sufficient fuel for flight. A fuel test on site and at the point of departure did not identify any visual contaminates, including water. In addition, fuel samples were collected from the helicopter and departure point fuel pump, for future chemical analysis testing if required. The engine and a majority of the airframe was retrieved from the accident site and transported to Alice Springs. The engine was then removed from the wreckage and transported to Brisbane for further examination under the supervision of the ATSB. Several components and cockpit warning lamps were retained for examination.
Weather and terrain
The accident site was within the MacDonnell Ranges at an elevation of about 1,850 ft, 31 km east of Ambalindum Station. At the time of the accident the weather forecast included moderate turbulence throughout the area. At 0800 the Alice Springs Airport recorded a wind speed of 18 kt, with gusts to 29 kt, from 330 degrees, and a temperature of 29 °C. The Arltunga weather station, located about 40 km west of the accident site, recorded two observations each day. At 0800 it recorded a wind speed of 14 kt[3] from 360 degrees, and a temperature of 30 °C.
Engine tests and inspections
On 8 and 9 January 2019, inspections and tests were conducted on the recovered engine. Representatives from the workshop, Civil Aviation Safety Authority, insurance company and helicopter owner were present.[4] No fault was identified that would have prevented normal engine operation. Damage to the engine cooling fan and the presence of dirt inside the number 2 cylinder indicated the engine was operating at the time of initial impact. Scoring damage to the V-belt actuator was identified. The helicopter manufacturer advised the ATSB that the identified damage was consistent with the upper sheave rotating on contact with the actuator as the structure distorted on impact and that the actuator was in the extended position.[5]
Further investigation
To date, the ATSB has examined the wreckage, interviewed witnesses, consulted with the helicopter manufacturer and collected weather data and analysis from the Bureau of Meteorology.
The ATSB will conduct further enquiries into:
flight planning
the weight and balance of the helicopter
examination of individual components and warning lamps
analysis of data recording devices
pilot training and qualifications.
The information contained in this update is released in accordance with section 25 of the Transport Safety Investigation Act 2003 and is derived from the initial investigation of the occurrence. Readers are cautioned that new evidence will become available as the investigation progresses that will enhance the ATSB's understanding of the accident as outlined in this update.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.