On 18 April 2022, the pilot of a Cessna 172 aircraft, registered VH-REU, was conducting a private flight at Coonabarabran Aerodrome, New South Wales.
After completing several circuits and touch-and-go landings, the pilot flew a low pass at 15–25 ft above the ground over a tractor that was being used to slash a field adjacent to the aerodrome. During the low pass, the aircraft contacted powerlines over the field and impacted terrain. The pilot received fatal injuries and the aircraft was destroyed
What the ATSB found
No pre-impact defects were identified with the aircraft structure, flight controls or engine, and witnesses stated the aircraft was operating normally on the day of the accident. Although operations at low levels are normal in the vicinity of an airfield during take-off and landing, the aircraft’s flight path just prior to the collision did not align with the runways and was not consistent with any part of a normal circuit pattern. It was therefore very likely that the pilot was conducting an intentional low-level pass over the tractor. The pilot was familiar with the aerodrome and was reported to be aware of the location of the powerlines. The pilot did not have a low-level rating and therefore had not undertaken the required training and assessment required to operate below 500 ft.
The pilot was wearing only the lap portion of the seatbelt during the accident flight, and not the sash-type upper torso restraint that was also fitted. However, it was not possible to determine with certainty whether, if worn, the upper torso restraint would have reduced the severity of injuries.
What has been done as a result
Based on a risk assessment conducted by the electricity provider post-accident, aerial safety markers were fitted to the powerlines in the field adjacent to the aerodrome where the aircraft contacted powerlines.
Safety message
Operations at low height expose an aircraft to several hazards like powerlines, which are typically very difficult to see and present a critical hazard to any low-flying aircraft. As identified in the ATSB publication Avoidable Accidents No. 1 - Low-level flying, research has shown that an awareness of powerline location does not guarantee avoidance. In recognition of these and the other specific risks and hazards of low-level flying, the Civil Aviation Safety Authority requires pilots to receive special training and a specific low-level rating before conducting low-level operations. Even with appropriate training, flying at low-level carries a significant risk and should be avoided when there is no operational reason.
Additionally, research has shown that wearing an upper torso restraint significantly reduces the risk of serious or fatal injury. Therefore, pilots should always wear upper torso restraints when available.
The investigation
Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 18 April 2022, the pilot of a Cessna 172, registered VH‑REU, was conducting a private flight involving circuits[1] and touch-and-go landings[2] at Coonabarabran Aerodrome, New South Wales. The pilot was the only person on board.
The pilot had been at the aerodrome the day prior, and it was reported by a friend (who had known the pilot for a significant period) that a discussion took place about a newly-erected gate, installed to permit access to a field adjacent to the aerodrome. Part of the discussion included the position of the gate, and that it had been installed in a different location than originally decided because of its proximity to overhead powerlines.
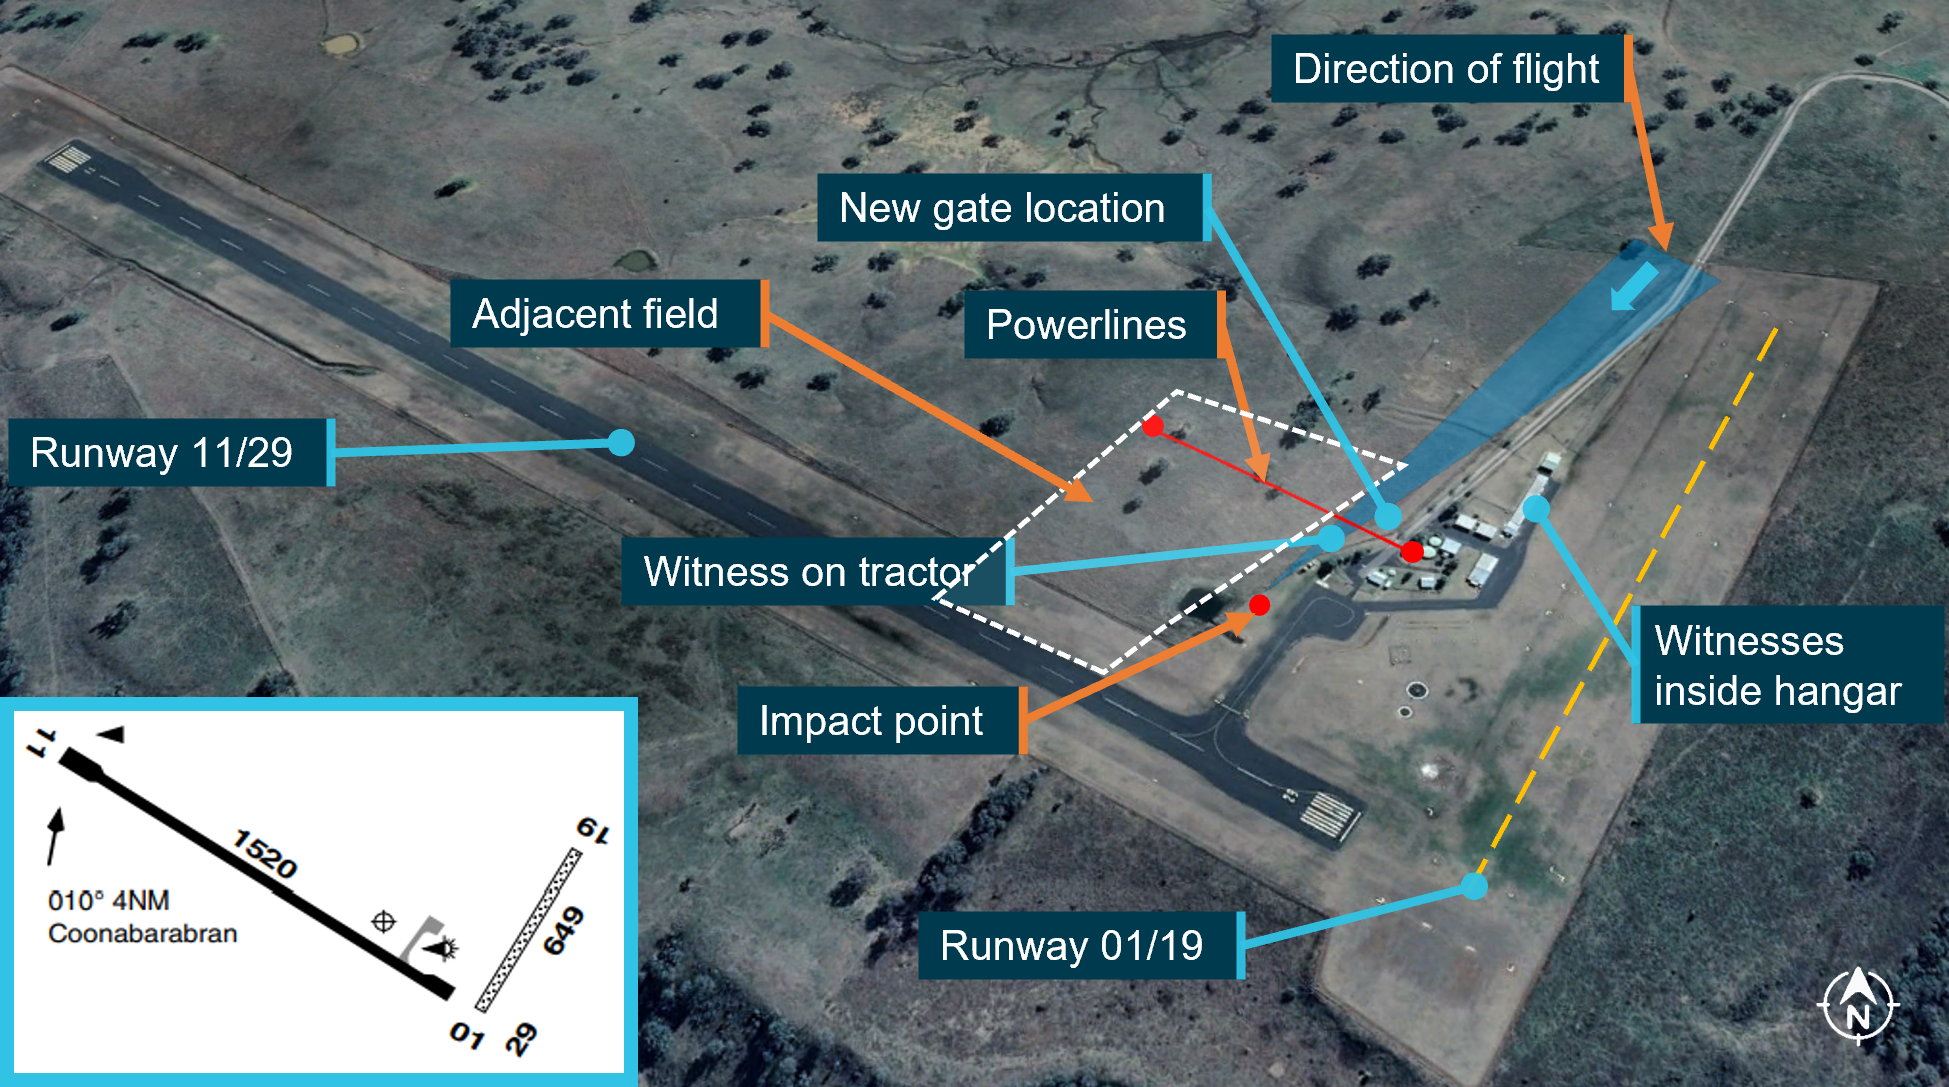
On the day of the accident, the pilot arrived at the aerodrome at about 1530 local time. Four other people were at the aerodrome: 3 in a hangar and the friend—who was the person who had talked with the pilot the day before—on a tractor that was towing a slasher in the adjacent field (Figure 1). One of the witnesses in the hangar recalled seeing the pilot take off to the north on runway 29.
The witness on the tractor recalled seeing the pilot do 2 touch-and-go landings on runway 11, before travelling to the north behind the witness, and banking right back towards the aerodrome. At the time, the witness initially thought that the pilot may have been going to conduct an approach to runway 19, but then realised that this was probably not the case as the aircraft was not turning left, which would have been normal for the approach to runway 19.
Figure 1: Aerodrome and flight path overview
Inset: En Route Supplement Australia (ERSA) chart of Coonabarabran Aerodrome, showing runway lengths in metres.
Source: Google Earth, annotated by the ATSB. Inset: Airservices Australia
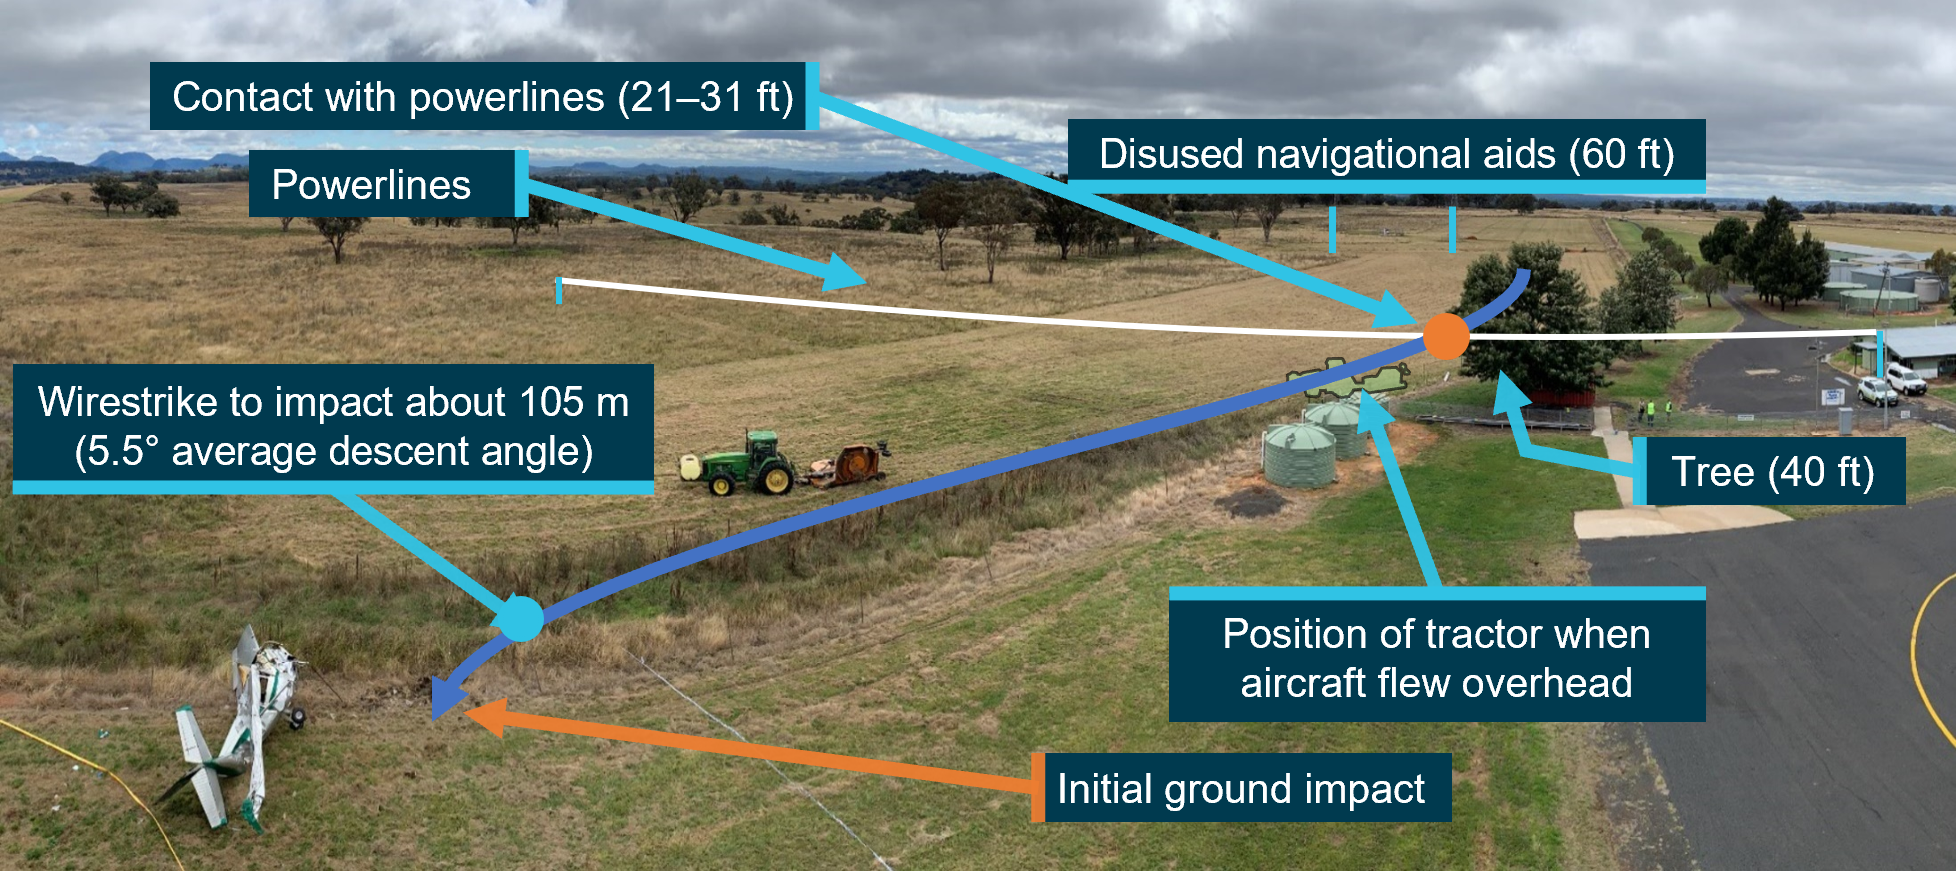
The witness on the tractor recalled that the next time they saw the aircraft, it was about 500 m away and was travelling back towards the field at about 70 ft (or about the same height as some unused navigational aids) (Figure 2). At this time, based on the direction and height of the aircraft, the witness thought that the pilot was likely going to fly directly over the tractor. When the witness turned again, the aircraft was directly behind them, flying straight and level. The witness estimated its speed as about 80–85 kt, or fast enough to maintain control of the aircraft but not at top speed. The witness observed the aircraft contact the powerlines just behind and above the tractor and recalled hearing a whistling and crack as the wires travelled over the tractor cab.
Figure 2: Estimated flight path based on impact with powerlines and witness account
Flight path of VH-REU indicated by blue line.
Source: ATSB
The witnesses inside the hangar recalled hearing the aircraft fly past the back of the hangar with the engine sounding like what one of the witnesses described as ‘high power’. Not long after, electrical power to the hangar was lost.
After the aircraft contacted the powerlines, it impacted the ground at a steep angle, cartwheeling to the right and coming to rest just inside the boundary fence of the aerodrome. The pilot was fatally injured, and the aircraft was destroyed.
Context
Pilot information
The pilot held a valid private pilot licence (aeroplane), issued in 1994 and with class ratings for multi- and single- engine aeroplanes. The pilot did not hold a low-level rating or any other operational ratings. In August 2019, the pilot reported during an aviation medical examination, that they had accumulated 2,655 flight hours. The pilot’s flight hours at the time of the accident could not be determined.
In addition to obtaining their private licence, the pilot had been involved in several aviation activities throughout their career, including involvement in aerial firefighting (in non-piloting aerial support roles) in a rotary-wing context.
The pilot held a class 2 medical certificate, valid to 30 September 2023, with no identified medical conditions. The pilot was required to have reading correction available to exercise the privileges of the licence. There were no issues identified in the post-mortem examination and toxicological results (including carbon monoxide) that may have affected the pilot’s operation of the aircraft. The pilot was also reported to have slept well in the days leading up to the accident and be in good general health.
Aircraft information
The Cessna 172 is a high-wing, all-metal, unpressurised aircraft with a fixed landing gear. VH‑REU had a single, Continental O-300-A piston engine driving a fixed-pitch propeller.
VH-REU was manufactured in 1958 with serial number 46237 and first registered in Australia in 1959. The aircraft had been owned by and registered to the pilot since 2016, and at the time of the accident had accumulated 1,046.3 hours total time in service.
The most recent maintenance for the aircraft was completed in April 2022 with a current maintenance release issued on 6 April 2022. The primary purpose for the maintenance was to complete a periodic (100–hourly) inspection and have a BendixKing Aerocruze autopilot fitted to the aircraft. In the days following installation, 2 flights totalling 2.1 hours were undertaken by the maintenance provider to check and adjust the autopilot. The only subsequent flight was a 0.9-hour flight by the owner on 14 April 2022.
Wreckage and impact information
No pre-impact defects were identified with the aircraft’s engine, flight controls or structure. There was no evidence of fire.
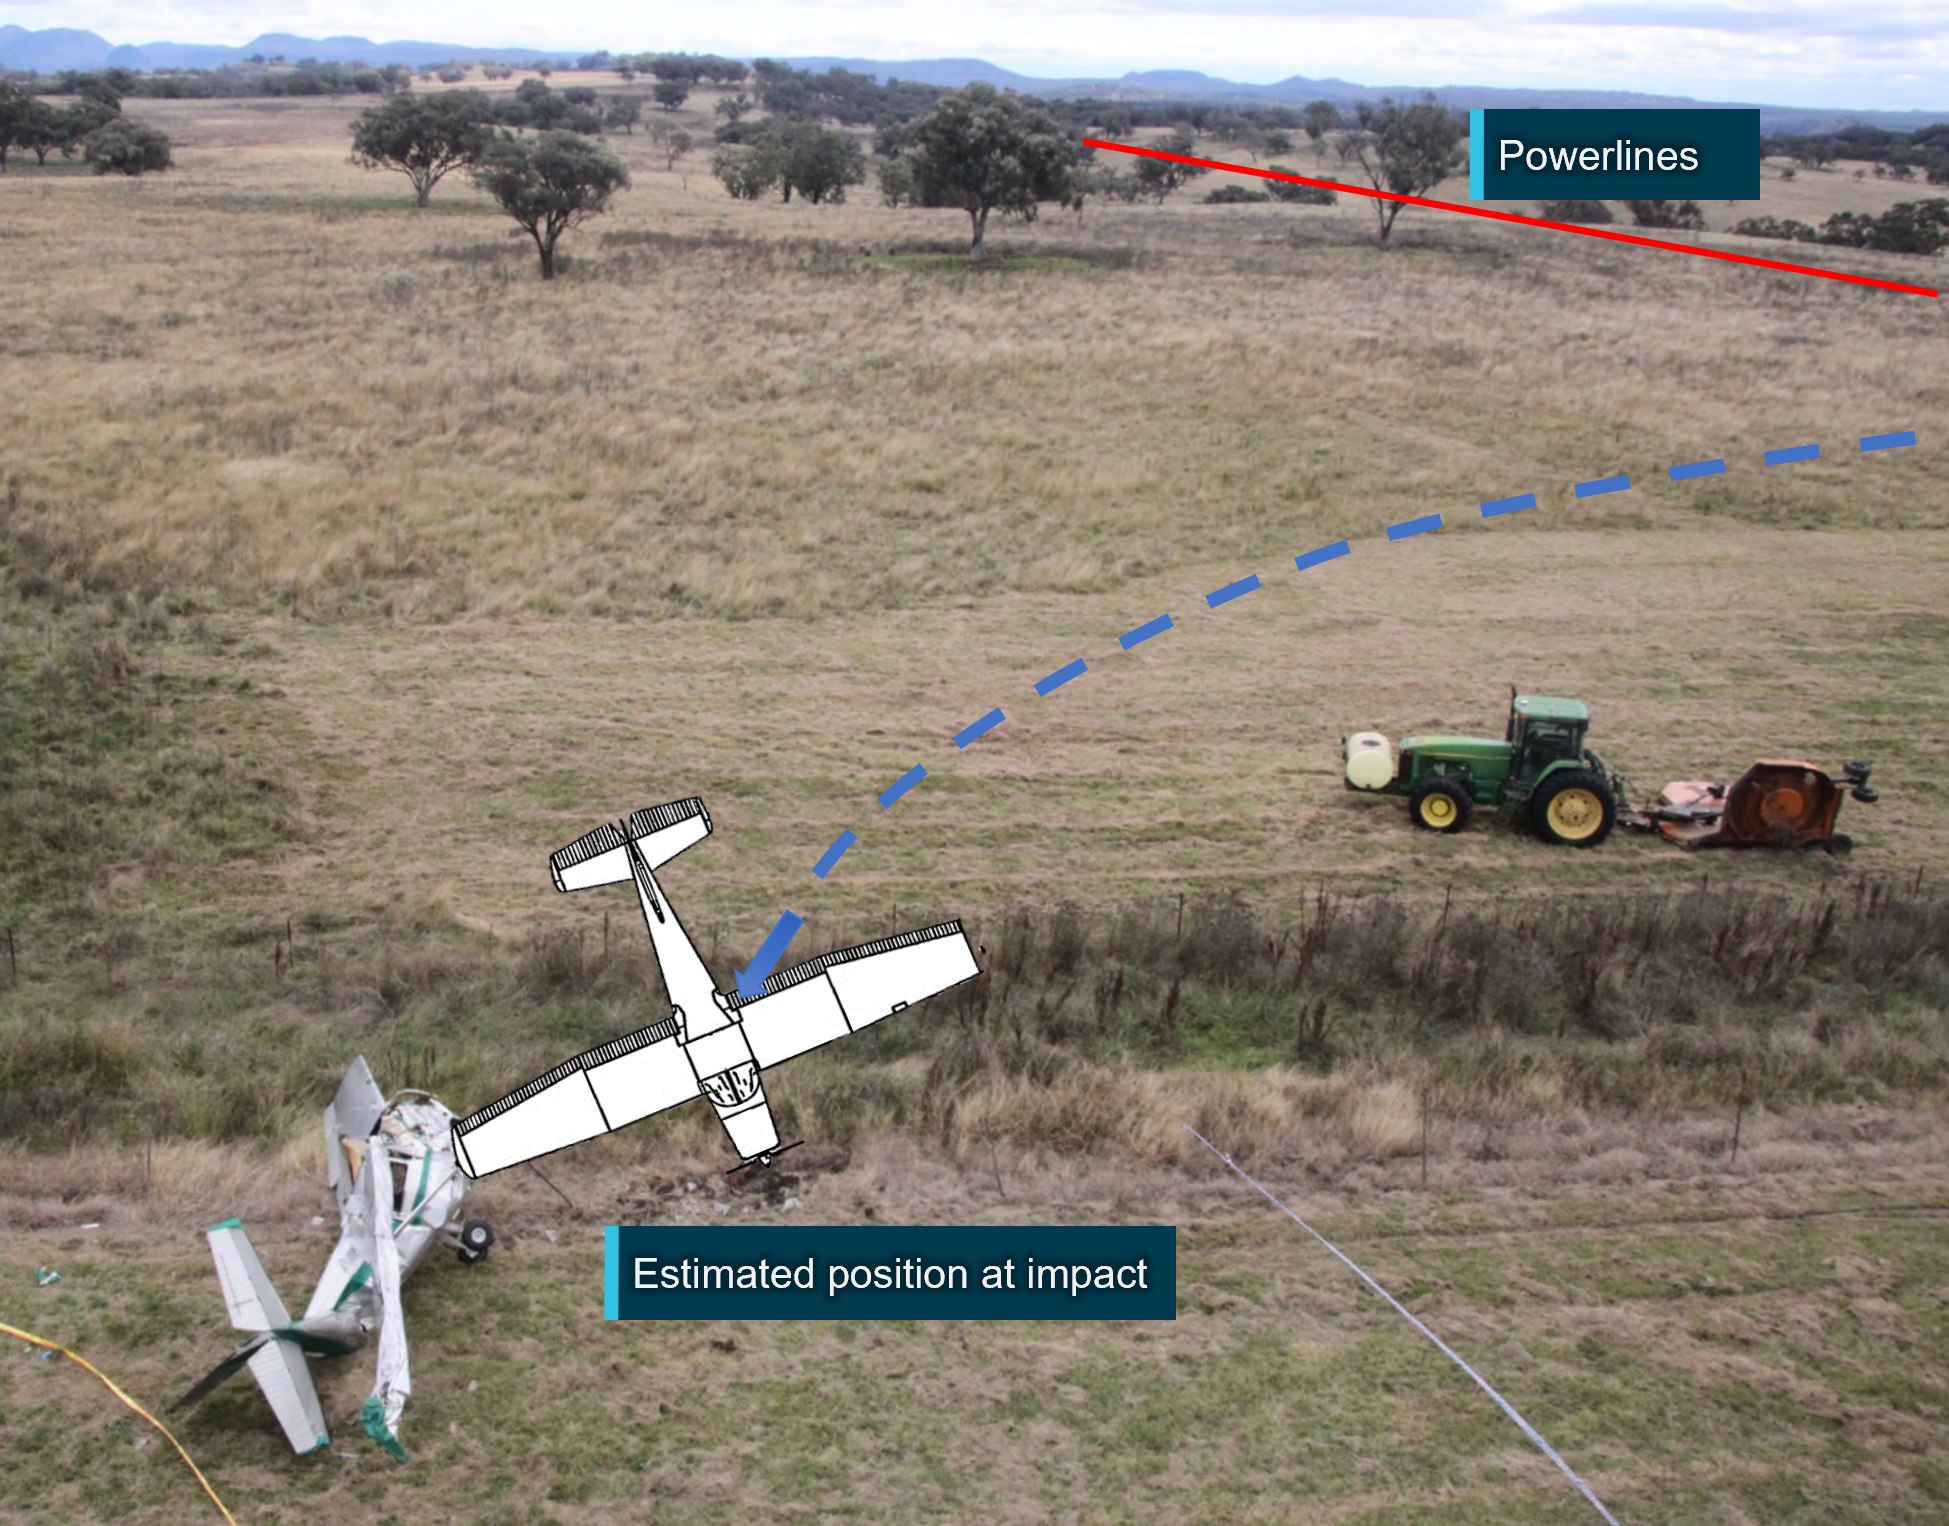
Damage to the aircraft and powerlines indicated that the aircraft had contacted the powerlines and then travelled about 105 m before ground impact. The aircraft impacted the ground about 57° nose-down, skidding to the right, and yawing to the left (Figure 3).
Figure 3: Estimated impact orientation
Source: ATSB
Based on a transfer of material from the airspeed indicator needle to its face, the aircraft likely impacted the ground at about 30 kt (or about 55 km/h) (Figure 4).
Figure 4: VH‑REU airspeed indicator with material transfer
Source: ATSB
The wreckage examination also showed:
damage to the left wing and strut indicated that the aircraft was likely close to level flight (about 11–12° right wing low) when it contacted the powerlines, with one of the powerlines remaining entangled with the left wing and left wing strut (Figure 5)
one of the propeller blades had marks likely from contact with the powerlines, and had a significant forward bend and tip curl, which was consistent with the engine producing power when the aircraft impacted the ground (Figure 6)
the other propeller blade was bent rearwards and had damage consistent with ground impact during the cartwheeling motion of the aircraft
liveable space in the cabin was maintained
the seat tracks were in place and the pilot’s seat was still attached to the aircraft structure
the pilot’s upper torso restraint (shoulder harness) was found stowed.[3]
Figure 5: Powerline, left wing and strut
Source: ATSB
Figure 6: Damage to propeller from powerlines and ground impact
Source: ATSB
Meteorological conditions
The aerodrome forecast (TAF) for Coonabarabran Aerodrome issued on 18 April 2022 and valid from midday included a forecast wind 350° at 12 kt, visibility more than 10 km, scattered cloud at 3,000 ft and temperature of 22 °C. Actual conditions at about the time of the accident were consistent with the forecast and indicated a temperature of 23° C, wind 360° at 7 kt, nil cloud with visibility greater than 10 km.
Aerodrome information
Coonabarabran Aerodrome was a certified, non-controlled aerodrome. It had a 1520-m long asphalt runway 11/29[4], and a 649-m long grass runway 01/19.
The normal circuits for all runways at Coonabarabran had left-hand patterns (turns made in the circuit were to the left).
Powerline information
The 22-kV powerlines that were struck by the aircraft consisted of a pair of 3-strand galvanised steel wires. The wires spanned across timber poles that were 314 m apart. The powerlines had to be maintained so that the wires had a clearance of 5.5 m from the ground. The powerlines at the aerodrome (including an allowance for catenary) were reportedly compliant with this requirement, and were estimated to be at a height of 21–31 ft (6–9 m) above the ground at the point of impact at the time of the accident. The nearest power pole was a terminus of the line that ran to the aerodrome (Figure 1).
The powerlines were not marked and were not required to be marked by Australian Standards (AS) 3891.1 (Permanent marking of overhead cables and their supporting structures for other than planned low level flying) or AS 3891.2.4 (Marking of overhead cables for planned low level flying operations, addressed the requirements for marking overhead cables, including powerlines).
Separately, the Civil Aviation Safety Authority detailed restrictions in the Civil Aviation Safety Regulations (CASR) Part 139 Manual of Standards (MOS) in relation to obstacles around an aerodrome. The adjacent field was located in the area defined as the aerodrome’s outer horizontal surface. In this area, markings were required on any object that was 150 m or higher. Markings were also required on any object in the take-off or approach path of aircraft. Neither of these requirements applied to the powerlines located at Coonabarabran Aerodrome.
Figure 7, looking west-north-west, shows reinstalled powerlines above the field after the accident.
Figure 7: Reinstalled powerlines in the adjacent field
Source: ATSB
Low-level rating
CASR 91.267 stated that a pilot could not fly below 500 ft (above the highest feature or obstacle within a horizontal radius of 300 m of the point on the ground or water immediately below the aircraft) unless in certain circumstances. These circumstances included (but were not limited to) the aircraft being in the process of taking off, landing or a missed approach, or the pilot holding an approval to conduct such flights.
The CASR Part 61 MOS required that, for pilots to obtain a low-level rating, which enabled them to undertake certain operations below 500 ft (such as agricultural, aerial survey or aerial firefighting), they must first demonstrate competency against certain performance criteria. In terms of operational techniques, this required (among other things) theoretical knowledge of how to manage obstructions such as powerlines and that a pilot could plan low-level operations, specifically identify hazards, evaluate and manage risks at low level.
Survivability
When assessing whether an aircraft accident is survivable, a number of aspects need to be considered, including:
forces imparted on the aircraft occupants
occupant restraints
liveable space inside the aircraft being maintained.
ATSB analysis indicated that the level of deceleration exerted on the pilot of VH-REU during ground impact was likely to result in severe or fatal injuries.
CASR 90.105 required that the seats in the front row of an aircraft be fitted with an approved safety harness. For small aeroplanes (with maximum take-off weight less than 5,700 kg), the safety harness needed to consist of a lap belt and at least one shoulder restraint (that is, a 3-point restraint).[5]
Upper torso restraints in aircraft serve 2 purposes:
to reduce upper body flailing and subsequent contact with aircraft structures and strike hazards
to distribute acceleration forces across a larger body area to reduce local transmission of force.
Although the upper torso section of a 3-point harness (with a sash-type upper restraint) provides restraint in the forward direction, it may provide very limited lateral restraint (Douglas and others 2007). Furthermore, if the occupant moves in a lateral (side) or diagonal direction away from the shoulder harness upper mounting point, it is possible to slip out of the shoulder harness.
VH-REU was fitted with 3-point restraints in each of the 2 front seats and the 2 rear seats. The pilot’s upper torso restraint was installed to cover the left shoulder. After the initial front-right impact, the pilot remained restrained by the lap belt. The upper torso restraint was not being worn.
Previous occurrences involving low-level flying and wirestrikes
ATSB educational publications discussing occurrences prior to 2013
The 2013 ATSB educational publication Avoidable Accidents No. 1: Low-level flying (AR‑2009‑041) focused on accidents involving unnecessary and unauthorised low flying:
Recognising the risks and hazards of low-level flying, CASA requires pilots to receive special training and endorsements before they can legally conduct low-level flying. In the accidents examined, many of the pilots did not have low-level training or an endorsement to do so, and none had a legitimate reason to be flying below the minimum limits. For most private pilots, there is generally no reason to fly at low levels, except during take-off and landing, conducting a forced or precautionary landing, or to avoid adverse weather conditions.
Another 2013 ATSB publication Avoidable Accidents No. 2: Wirestrikes involving known wires: A manageable aerial agriculture hazard (AR-2011-028) detailed a wirestrike accident where the pilot was aware of the powerline location:
Studies into ‘inattentional blindness’ have shown that we fail to perceive unexpected objects (even if they appear in the field of vision) if we are not paying attention to them (for example, focusing on another object or task). Without attention, there is no perception. Thus, you are unlikely to notice an approaching wire if you are not looking for it, even if you were previously aware of it. Add to this the inherent difficulty of visually spotting wires, the likelihood of hitting a wire is increased.
AO-2014-068 Wirestrike involving Maule M-5, VH-HOG, 50 km WSW of Casino NSW on 12 April 2014
On 12 April 2014, a Maule M-5 aircraft collided with a powerline spanning the Clarence River west-south-west of Casino, New South Wales. The pilot was accompanied on the private category flight by 2 passengers. The aircraft departed controlled flight after the wirestrike and impacted the water, coming to rest inverted with the cabin submerged. A child passenger was fatally injured.
The ATSB found that the pilot ‘made a spur of the moment decision to fly along an unfamiliar section of a river at very low level and collided with a powerline.’
AO-2014-131 Wirestrike and impact with terrain involving Cessna 182L, VH-TRS at Burrumbuttock, NSW on 20 July 2014
On 20 July 2014, a Cessna 182L aircraft collided with a powerline above a paddock. Prior to hitting the powerline, witnesses observed the aircraft flying at a low height. After hitting the powerline, the aircraft rolled inverted and impacted terrain. The pilot was fatally injured, and the aircraft was destroyed.
The ATSB found that the pilot did not hold an approval to fly at low level and therefore had not received any training in the identification of hazards or in operating techniques for flight close to the ground.
Previous occurrences involving not wearing upper torso restraints
The ATSB has conducted a number of investigations that found that pilots or passengers in the front seats of small aeroplanes that were fitted with upper torso restraints were not wearing the restraint. In all cases this increased the risk of serious or fatal injury and in some accidents, was found to have exacerbated the injuries received. Examples include:
AO-2010-053 Controlled flight into terrain - Cessna 210M, VHTIJ, 59 km NE Norseman WA, 13 July 2010
AO-2012-083 Collision with terrain, Cessna Aircraft Company 182P, VH-WTS, 53 km east-north-east of Cunnamulla, Qld, 19 June 2012
AO-2012-142 Wirestrike involving Cessna 172, VH-TKI, 13 km NE of Bendigo, Victoria, 29 October 2012
AO-2016-074 Loss of control and collision with terrain, Cessna 150, VH-RXU 270 km SE Alice Springs, Northern Territory, on 12 July 2016
AO-2019-002 Loss of power on take-off and forced landing involving Cessna 182, VH-DGF, Tooradin, Victoria on 6 January 2019.
Safety analysis
Intentional low-level flight
An examination of the wreckage found no pre-impact defects involving the aircraft structure, flight controls or engine. There were no recorded issues following flights undertaken to check and adjust the autopilot after its installation, or after the aircraft had returned to Coonabarabran.
Witnesses saw and heard the aircraft operating normally, other than the abnormal flight path. If the pilot had encountered a problem while conducting circuits, there were 2 runways available for an emergency landing. However, the flight path did not align with an approach to either runway. Based on the tractor driver’s observations, the aircraft was heading directly overhead the tractor, flying straight and level at a height of about 70 ft and at a normal speed. Therefore, it was unlikely that a mechanical or other operational problem was involved.
The height of the powerlines was about 21–31 ft (6–9 m) where the impact occurred, and the aircraft was therefore at a height above the ground of about 15–25 ft at the time (allowing about 6 ft for the impact point on the wing). There was no apparent operational reason for the pilot to have been flying at such a low height over the field other than to conduct an intentional overflight of the tractor and its driver. Given the absence of operational reasons or the low flight, and the witness’s observation of the aircraft just prior to the contact with the powerlines, it is likely that the pilot was flying at low-level with an intention of flying directly overhead the friend in the tractor.
Low-level rating
The pilot did not have a low-level rating, which requires specific training on hazard identification and flying techniques when operating at low-level. Generally, a low-level rating is required for occupations or operations where there is a requirement or purpose to be flying below the minimum permitted height, that is below 500 ft. Examples of activities that would require this include agricultural, aerial survey or aerial firefighting and provide a balance between operational necessity and risk.
Although the pilot had previous exposure to low-level flying (aerial firefighting), it was not as a pilot. The pilot did not hold a low level rating and had not undergone the required training and assessment for low level flying which may have better equipped them to identify potential hazards (such as powerlines). Even with the appropriate training, flying at low levels carries a considerable risk and should be avoided when there is no operational reason.
Powerline strike
The pilot was familiar with the aerodrome and had discussed the location of the powerlines the day prior to the accident. However, even if a pilot is aware of powerline locations, this does not guarantee avoidance. There have been several previous accidents whereby pilots who have known the location of powerlines have forgotten about them. Given the difficulty to see powerlines, there is often insufficient time to react and avoid them.
The location and height of the powerlines at Coonabarabran Aerodrome meant that they were not required to be fitted with markers and they would have been very difficult to see from the air. Had markers been fitted, the pilot may have seen the powerlines earlier. Nevertheless, the powerlines were not close to any area that an aircraft would have an operational reason to be operating.
Upper torso restraints and survivability
Research by the United States National Transportation Safety Board (NTSB) and others has shown that pilots wearing the lap portion of a seatbelt only are more likely to receive a serious or fatal injury. An NTSB study published in 2011 examined the effectiveness of upper torso restraints on pilots in small aeroplanes. The study found that a pilot would be 49% more likely to receive a serious or fatal injury when wearing a lap belt only, compared to those wearing both the lap belt and upper torso restraint.
The pilot of VH-REU was not wearing the aircraft’s sash-type upper torso restraint (mounted above the pilot’s left shoulder) at the time of the accident. However, the significant right yaw at impact would have limited the effectiveness of this type of upper torso restraint. Therefore, it was not possible to determine with certainty whether, if worn, the upper torso restraint would have reduced the level of injuries in this case. Nevertheless, in many other types of accident scenarios, wearing an upper torso restraint will significantly reduce the risk of injury.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the wirestrike and collision with terrain involving Cessna 172, registration VH-REU, on 18 April 2022.
Contributing factors
While the pilot was conducting a low pass at a height of 15–25 ft over a field adjacent to the aerodrome, the aircraft contacted powerlines and collided with terrain.
Other factors that increased risk
The pilot was not wearing an upper torso restraint during the accident flight, increasing the likelihood of serious injury in a collision.
Other findings
The pilot did not have a low-level rating, which requires specific training on hazard identification and flying techniques when operating at low level.
The powerlines that were contacted by the aircraft were not fitted with a visual marker and given the height and location of the powerlines, there was no requirement for such markers.
Safety actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Safety action by Essential Energy
Following the wirestrike accident involving VH-REU and in accordance with its company policy, Essential Energy field workers assessed the risk of another wirestrike to the powerlines that crossed the fields north of Coonabarabran Aerodrome. Subsequently, Essential Energy installed aerial markers to these powerlines.
Sources and submissions
Sources of information
The sources of information during the investigation included:
the witnesses
the NSW Police Force
the Civil Aviation Safety Authority
the maintenance provider for VH-REU
Essential Energy
Warrumbungle Shire Council (aerodrome manager).
References
Douglas CA, Fildes BN, Gibson TJ, Boström O & Pintar FA 2007, ‘Factors influencing occupant-to-seat belt interaction in far-side crashes’, Annual Proceedings of the Association for the Advancement of Automotive Medicine, 51:319–39.
National Transportation Safety Board 2011, Airbag performance in general aviation restraint systems, Safety Study NTSB/SS-11/01.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the Civil Aviation Safety Authority (CASA)
Essential Energy
the maintenance provider for VH-REU
Warrumbungle Shire Council.
Submissions were received from CASA and Essential Energy. The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Circuit: the specified path to be flown by aircraft operating in the vicinity of an aerodrome.
[2] Touch-and-go: a manoeuvre in which an aircraft conducts an approach, touches the runway, and immediately takes off again.
[3] The upper torso restraint (shoulder harness) was physically attached to the roof of the cabin at one end, and when in use, the other end is secured to the lap portion of the restraint.
[4] Runway numbering: represents the magnetic heading closest to the runway orientation (for example, runway 29 is oriented 292º magnetic).
[5] The shoulder harness and/or restraint is referred to as an upper torso restraint in this report.
On 16 April 2022, at approximately 0805 local time, the pilot of Beechcraft B58 Baron aircraft registered VH-NPT commenced a straight in approach to runway 12 at the East Kimberley Regional Airport with one passenger and 4 boxes of cargo on-board. The pilot reported that when they attempted to extend the landing gear they received multiple unusual indications, followed by an electrical burning smell, and saw smoke emerge from forward of the pilot’s circuit breaker panel near their left leg.
The pilot made a PAN-PAN call to air traffic control, activated the SOS function on the dash mounted Spider Tracks unit and recalled switching off electrical power. By this time flames were emerging from where the smoke had previously been observed. The pilot then expended the entire contents of a handheld portable fire extinguisher, however the fire quickly returned and intensified.
Flames and thick smoke filled the cockpit preventing the pilot from effectively seeing external visual references or the aircraft’s flight instruments. The aircraft subsequently diverged from the runway centreline track and collided with terrain approximately 800m from the threshold of runway 12.
Following the collision, the pilot extricated themselves from the inverted aircraft. The pilot then re‑entered the aircraft and, with limited assistance from the semi-conscious passenger, extracted them from the aircraft before it was consumed by a significant post impact fire. The passenger succumbed to their injuries and the pilot received serious injuries.
What the ATSB found
The ATSB determined that a fault associated with the landing gear electrical system likely ignited fuel from the cabin heater supply line, resulting in a significant and sustained cockpit fire.
The ATSB also determined that the pilot’s injuries were likely less severe due to the use of a 4‑point restraint. Additionally, while not required by regulation, the use of a rearward facing passenger seat is likely to reduce the severity of frontal impact‑related passenger injuries.
What has been done as a result
In response to this accident the operator reported that they:
commenced a program to install 4-point restraints in the crew seats of all their B58 aircraft
installed an additional fire extinguisher in each of their B58 aircraft
incorporated additional 100-hourly fuel line and wiring inspections in the vicinity of the heater fuel line and circuit breakers adjacent to the pilot’s seat.
The ATSB issued a Safety Advisory Notice encouraging operators of B58 aircraft to conduct a detailed examination of the wiring and heater fuel line on the left side of the aircraft, forward of and below the pilot’s circuit breaker panel.
Safety message
Damaged electrical wiring can pose a range of hazards to the safety of flight, including loss of electrical power, malfunctioning systems, and inflight fire. This hazard is further increased when wiring is proximal to lines carrying flammable liquid. Maintenance organisations and operators should review current practices for the prevention of damage to wiring and ensure that all available steps are being taken. These may include inspections, appropriate stand-offs, and utilisation of anti-chafe sleeving.
The ATSB continues to encourage the utilisation of devices that may increase the survivability in light aircraft accidents.
Four-point restraints, where available, provide increased survivability over 3-point restraints.
Where available and practical, use of rearward facing passenger seats improves frontal impact protection and survivability in an accident.
The occurrence
Pre-flight
In the morning of 16 April 2022, the pilot of a Beechcraft B58 Baron (B58) registered VH-NPT (NPT) arrived at Aviair Pty Ltd, at Broome Airport to prepare for a regular charter flight to several remote locations in northern Western Australia. The operator’s duty maintenance officer (maintainer) reported that the pilot contacted them by phone before the flight, reporting a ‘fuel kind of smell’ in the aircraft’s cockpit. The maintainer recalled discussing the basics of the aircraft’s fuel system and asking the pilot to monitor the situation and report back if the smell did not go away.
The flight
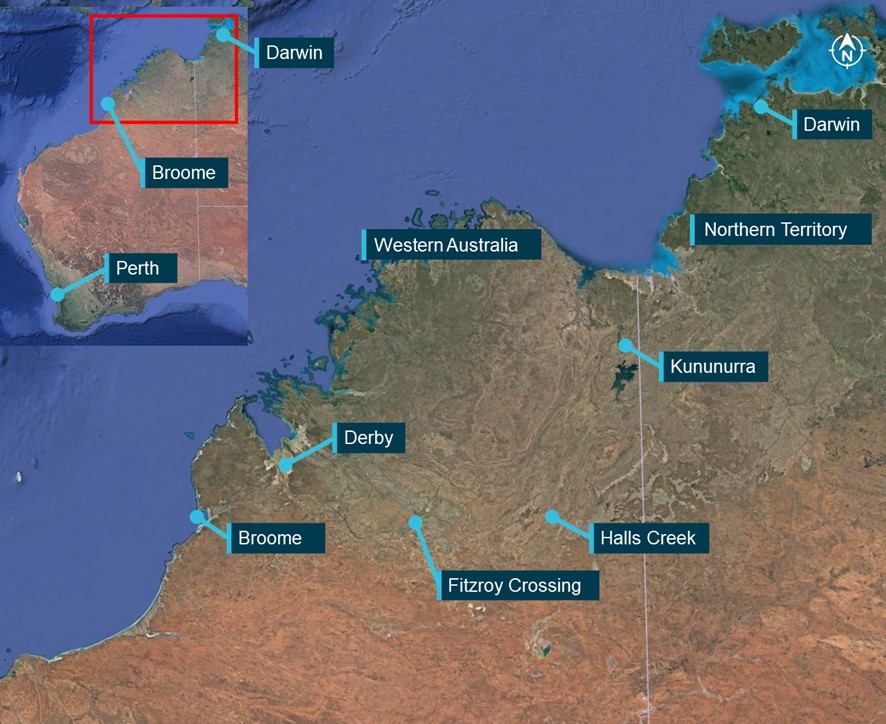
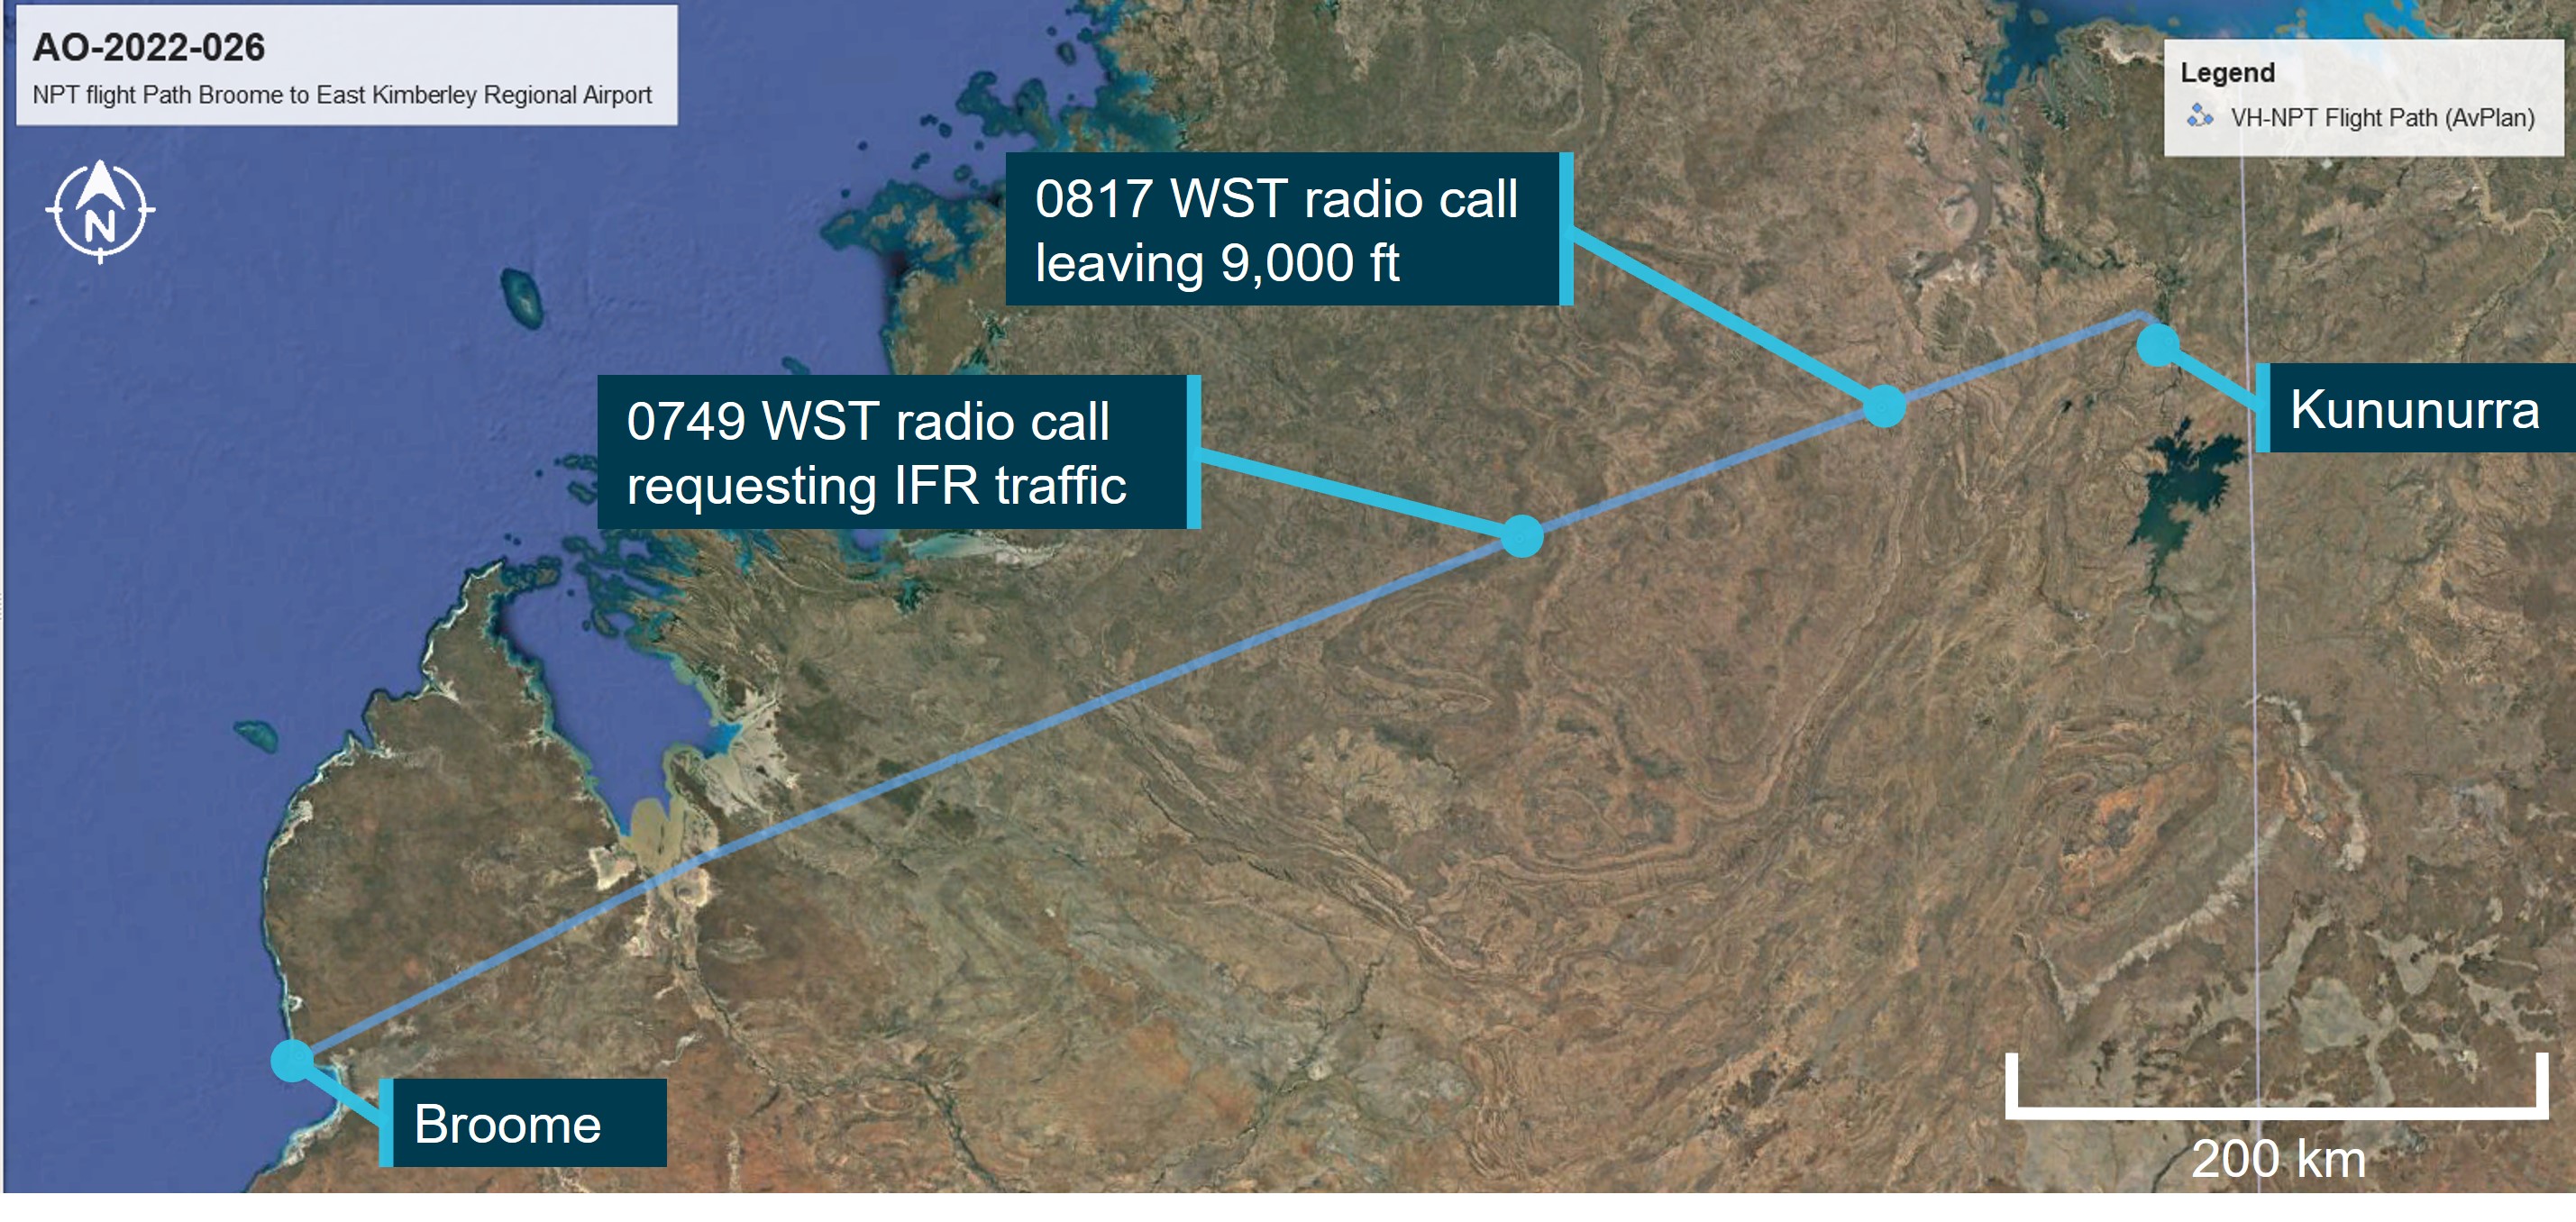
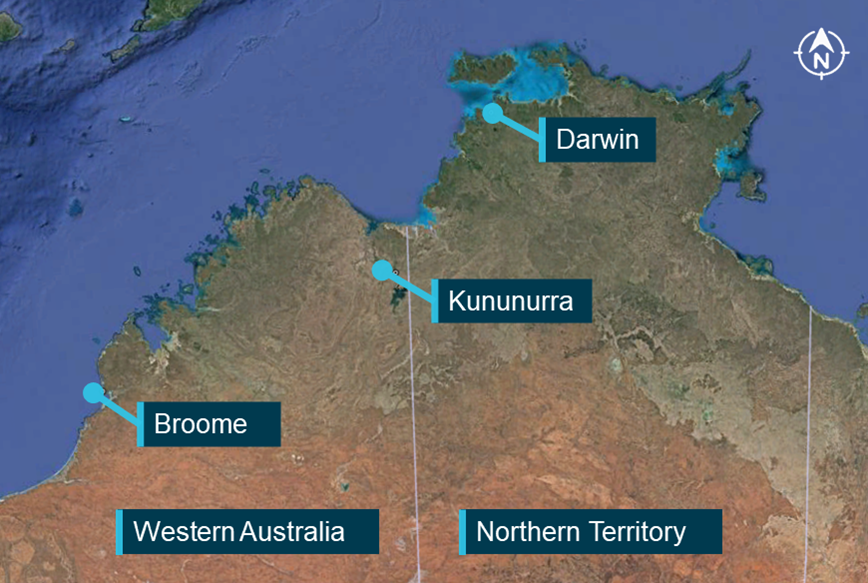
The flight, with one passenger, seated in the rear right seat, and 4 boxes of cargo onboard, was planned to transit through the East Kimberley Regional Airport at Kununurra (Figure 1), refuel, then continue to Halls Creek where the passenger was to disembark, Fitzroy Crossing to unload cargo and then return to Broome via Derby.
Figure 1: Flight area with planned stops
Source: Google Earth annotated by the ATSB
The aircraft departed Broome at 0613 local time and climbed to 9,000 ft while tracking to the north-east. The maintainer, reported that at 0628 the pilot contacted them again, advising that the ’fuel like smell’ detected on the ground was no longer present.
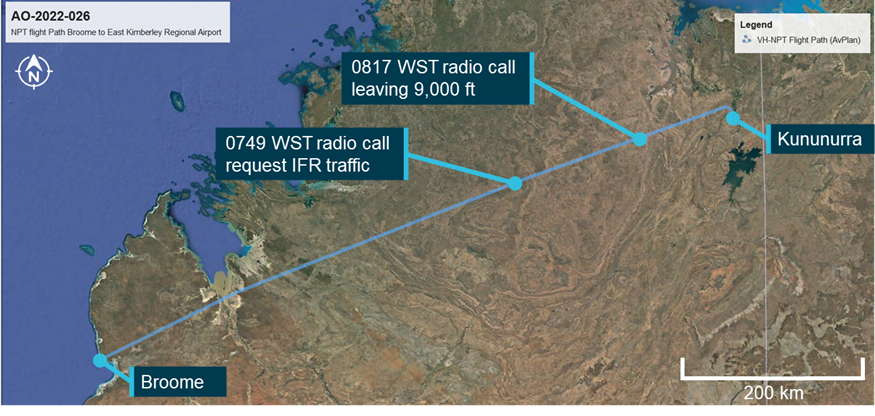
At 0749 the pilot contacted air traffic control (ATC) and requested traffic for a direct track to waypoint Kununurra Whiskey Foxtrot (KNXWF) for an approach to runway 12 at Kununurra (Figure 2). At 0817 the pilot of NPT contacted ATC advising that they were leaving their cruising altitude of 9,000 ft on descent for Kununurra.
Figure 2: NPT flight path and Brisbane Centre radio calls
Source: Google Earth and AvPlan annotated by the ATSB
The approach
Seventeen minutes later NPT joined a straight in approach to runway 12. The pilot recalled slowing the aircraft, extending the first stage of flaps, and attempting to extend the landing gear.
Upon selecting the landing gear handle to the down position, the gear down and locked indicators (3 green lights) illuminated immediately. The pilot reported that this was unusual, as normal operation required a few seconds for the landing gear to extend and the lights to illuminate. However, no sound was heard from the landing gear motor and no decrease in aircraft performance was felt that would indicate gear had extended. The pilot also recalled, co‑incident with the landing gear handle activation, that the landing gear warning horn erroneously activated. The pilot stated that these unusual indications were followed immediately by an electrical burning smell and smoke emerging from below the left side of the aircraft instrument panel, forward of the pilot’s circuit breaker panel.
About a minute later, at 0836, the pilot made a PAN-PAN[1] call on the Brisbane Centre frequency advising of smoke and suspected fire in the cockpit. The pilot then activated the SOS[2] function on a dash mounted Spider Tracks[3] unit. The pilot recalled switching off the electrical power to the aircraft, in accordance with the electrical smoke and fire emergency procedure. They also reported switching off the avionics master switch (see the section titled Electrical system) as an additional precaution. By that time flames were emanating from the same location as the previously observed smoke.
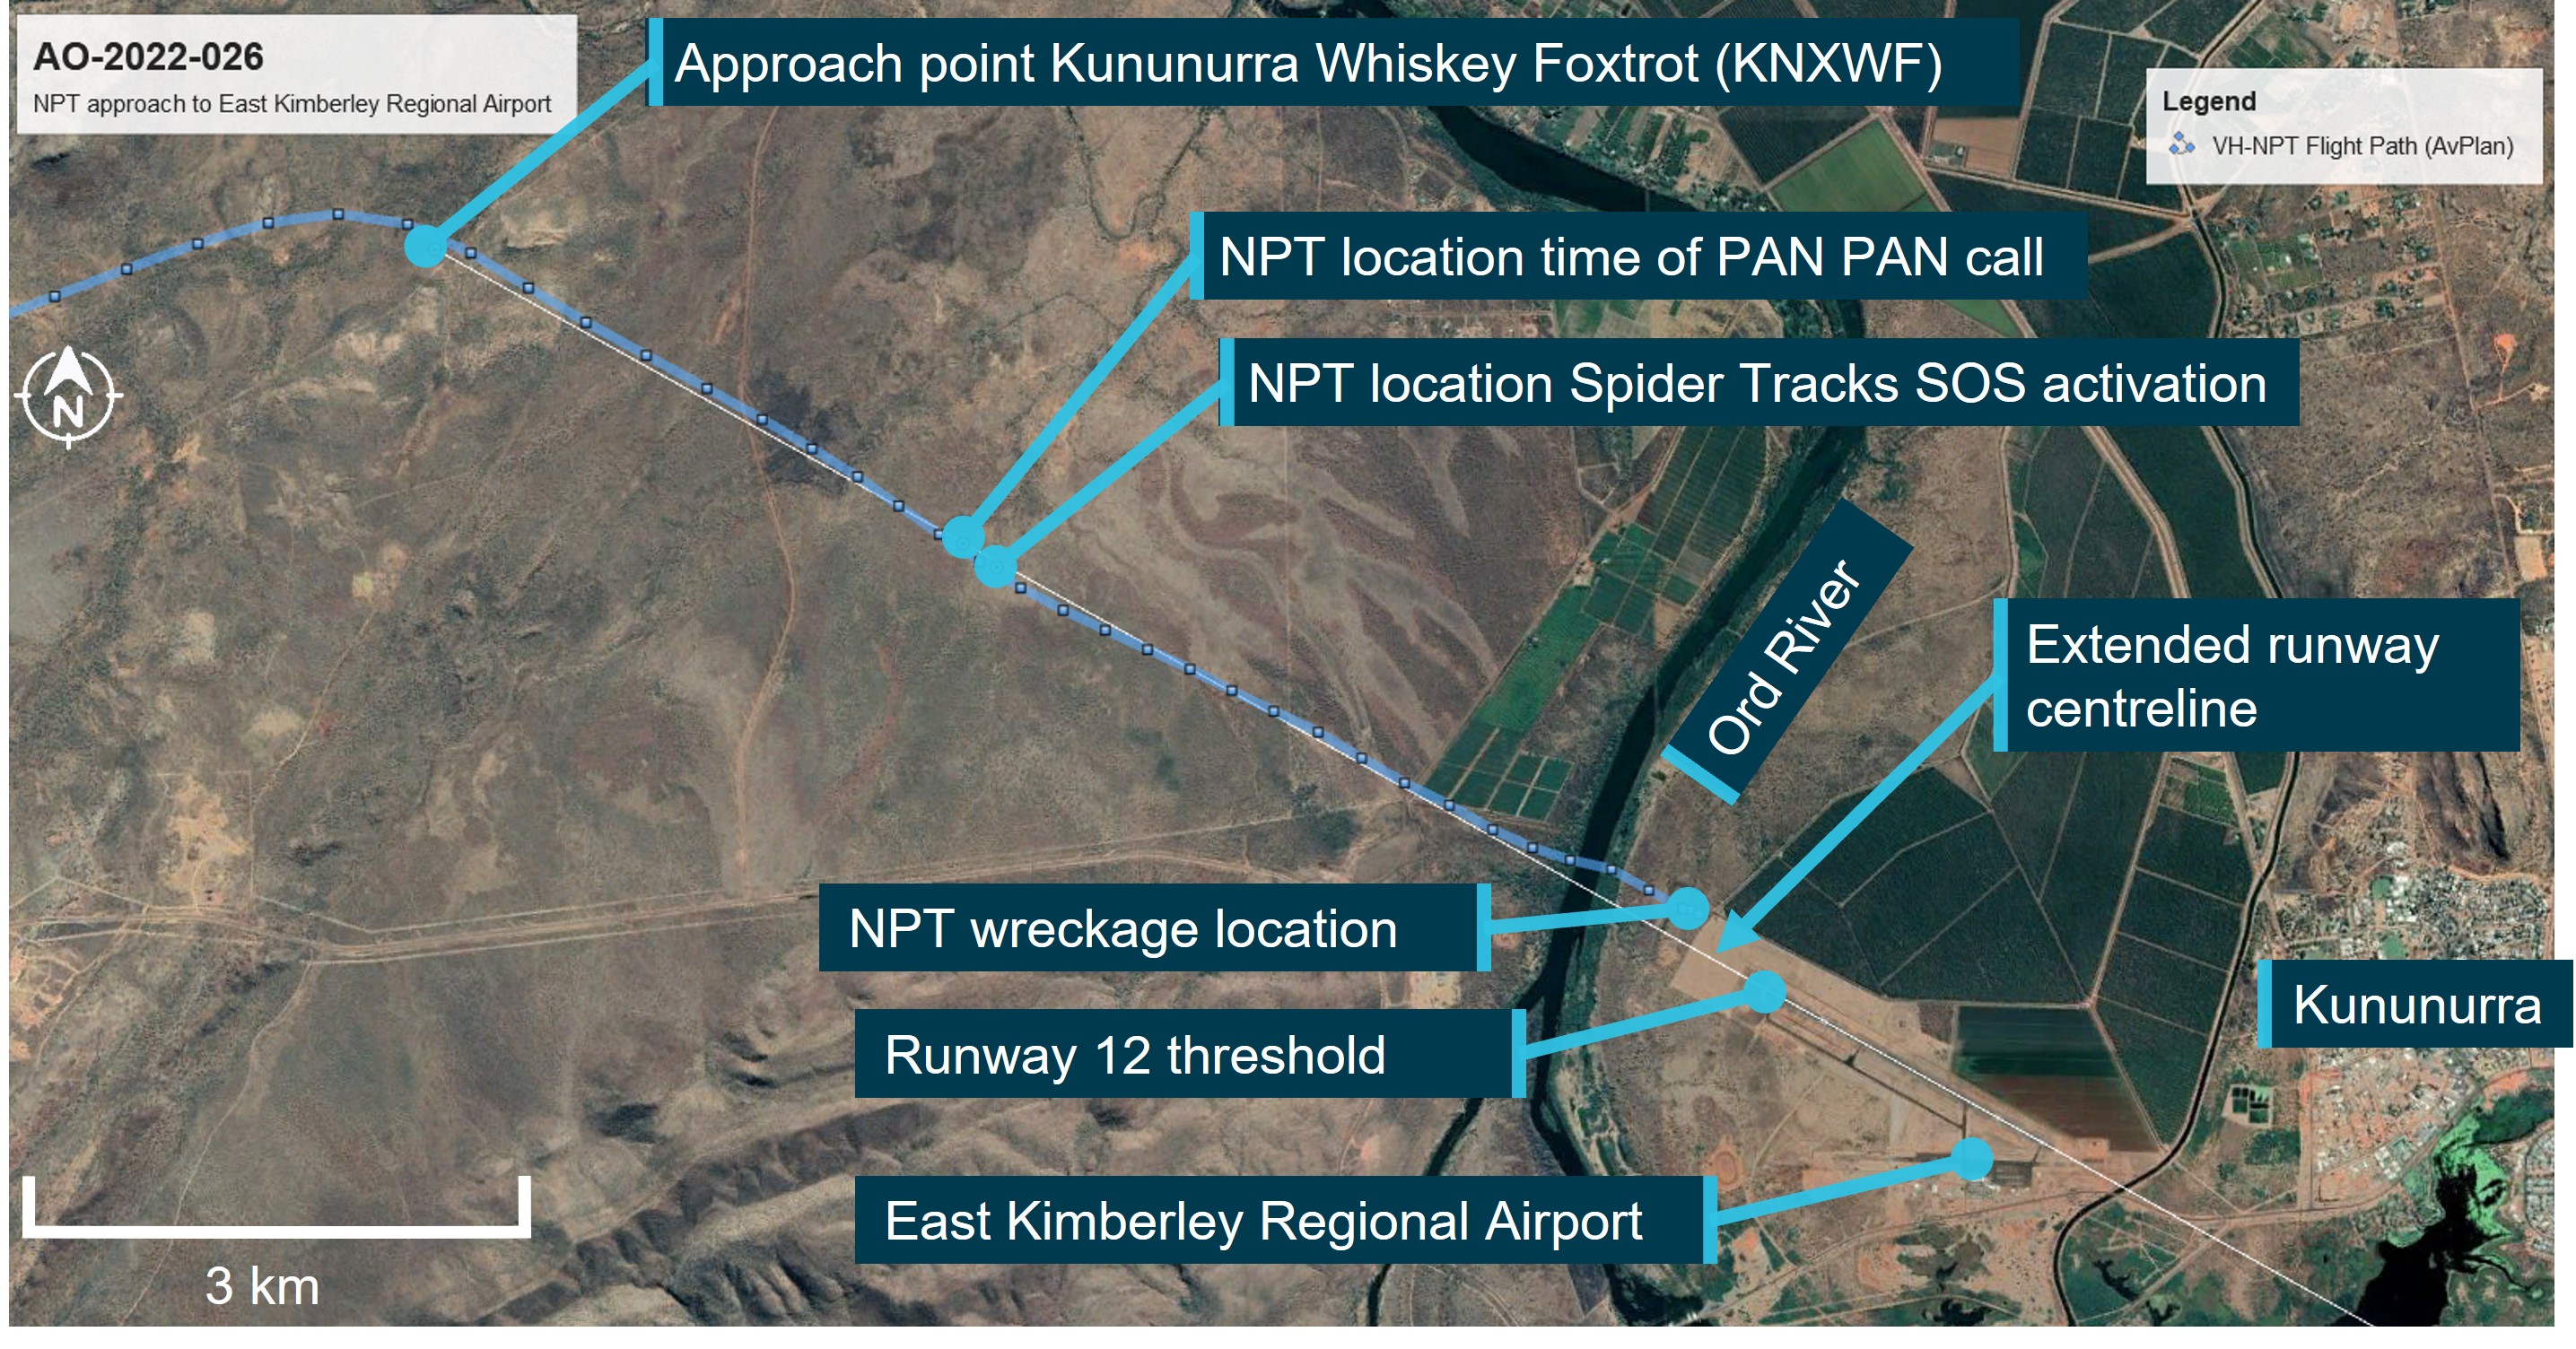
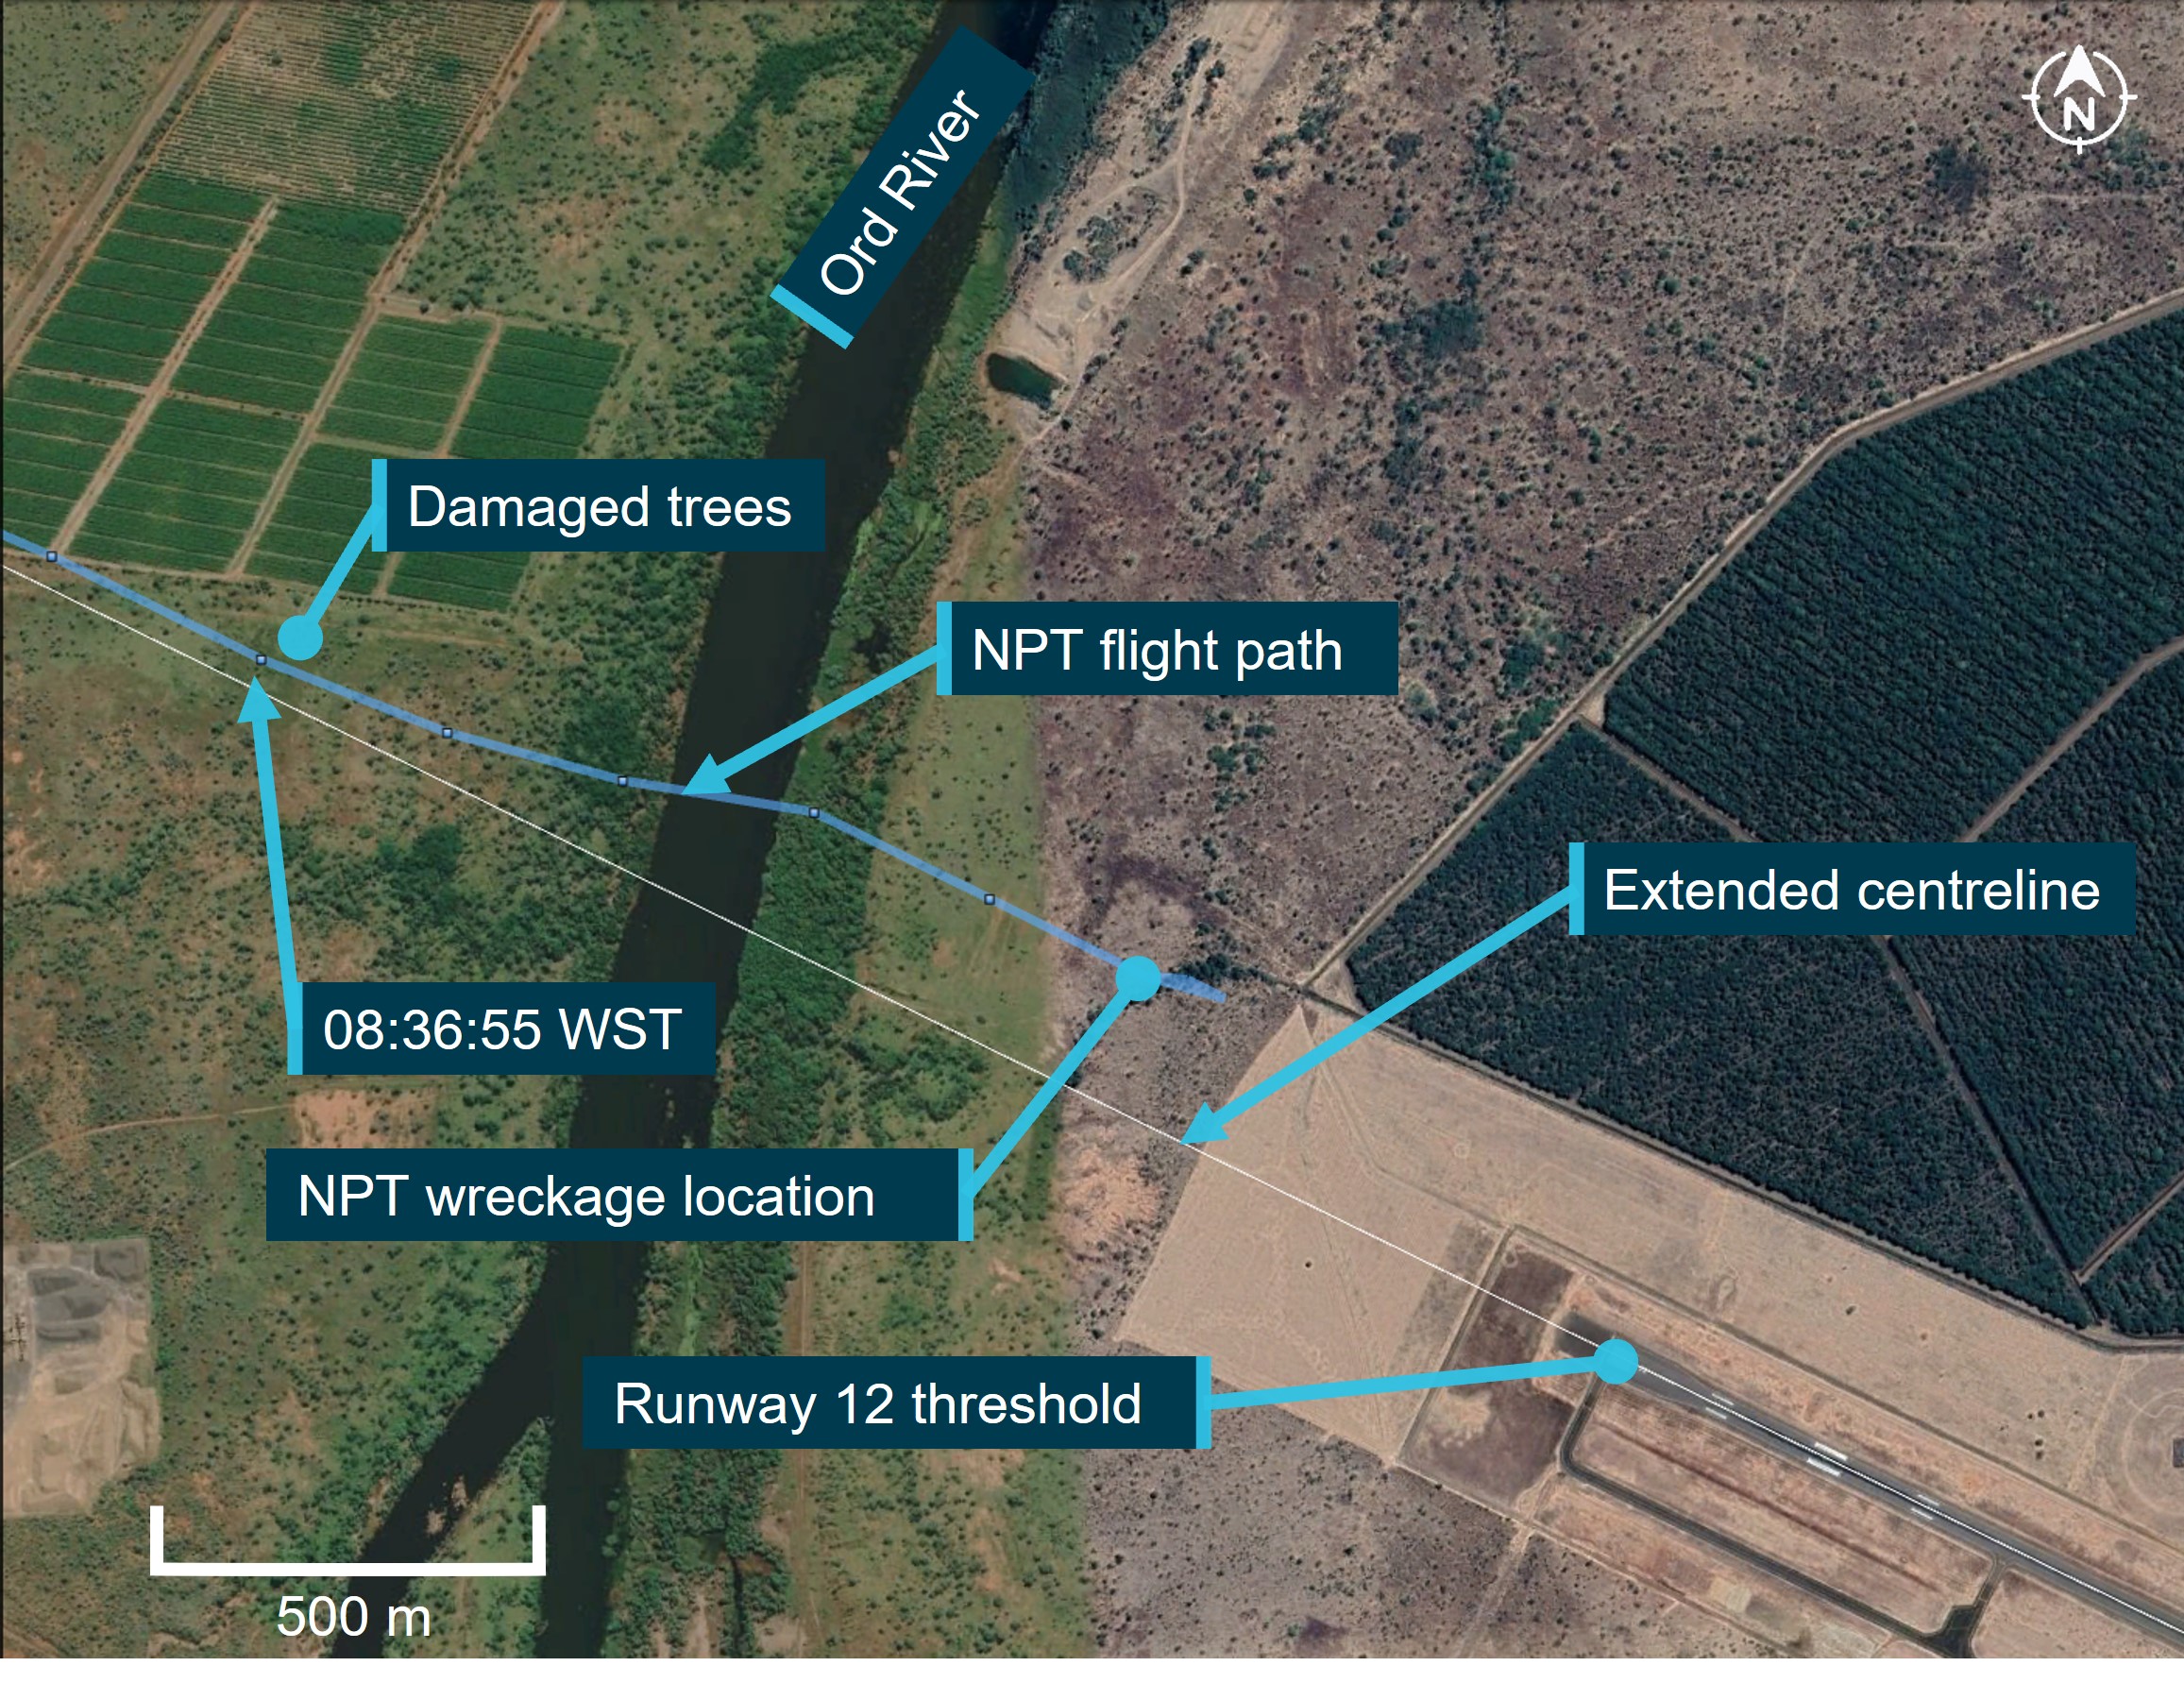
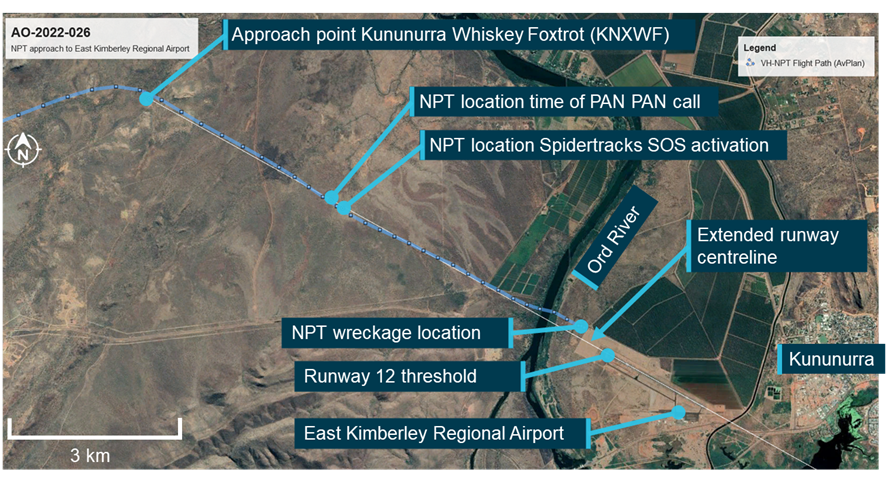
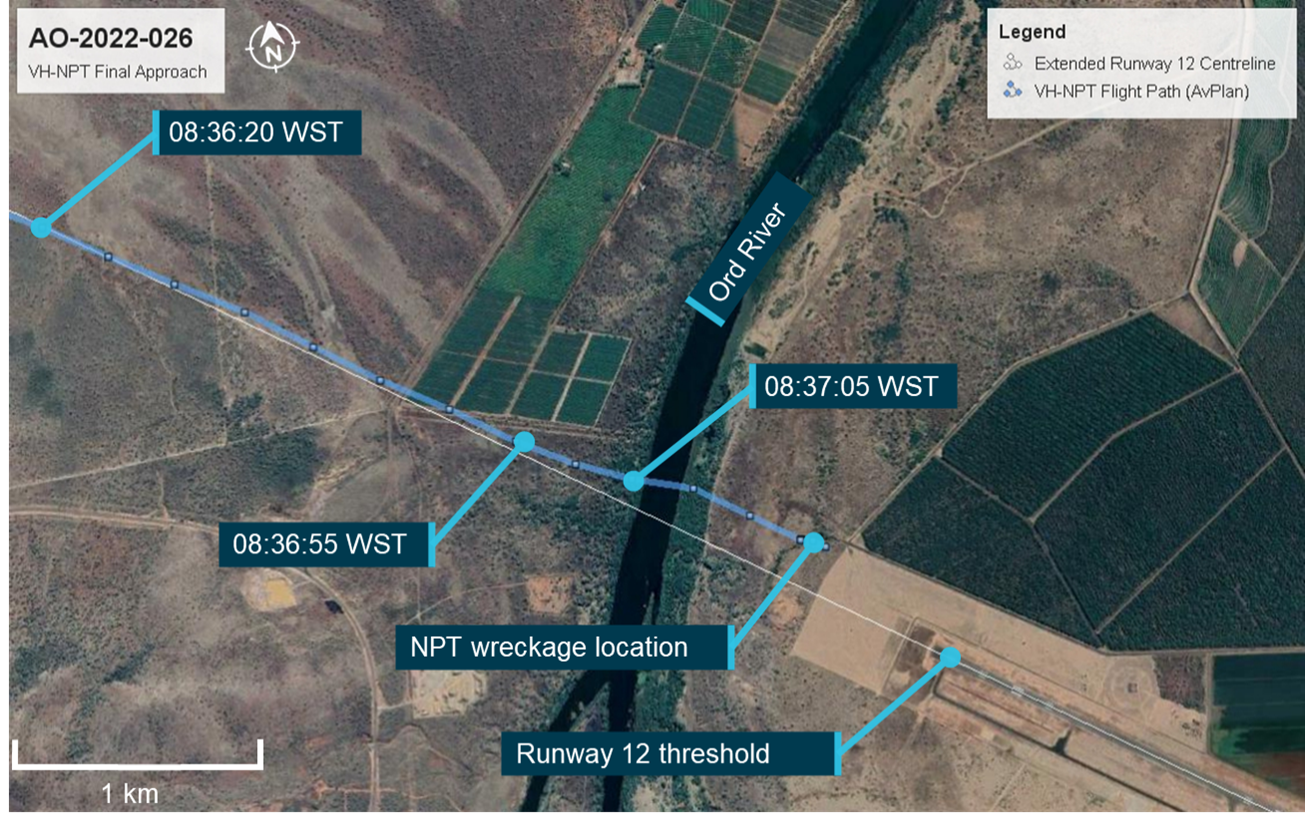
The pilot then expended the entire contents of the aircraft’s handheld portable fire extinguisher, while continuing the straight in approach to runway 12 (Figure 3). However, the fire almost immediately returned, emanating from the same location, with flame and significant smoke in the cockpit. The pilot reported difficulty maintaining control of the aircraft as their left hand and leg were exposed directly to the flames and the smoke prevented them seeing both the instruments and the outside environment. In response, they opened the aircraft’s storm window[4] in an attempt to clear the smoke and obtain a visual reference.
Figure 3: NPT approach to East Kimberley Regional Airport
Source: Google Earth, AvPlan and Airservices Australia, annotated by the ATSB
As the aircraft approached the Ord River, multiple airborne witnesses reported that it appeared to be below the standard approach profile and ‘skimming the treetops.’
Recorded flight data indicated that, at 0837, the aircraft started diverging left of the extended runway centre line, crossing the Ord River at low level approximately 1.5 km from the threshold of runway 12. The aircraft subsequently collided with terrain, coming to rest inverted about 600 m beyond the river and about 800 m from the runway 12 threshold (Figure 3) and was consumed by a significant post‑impact fire.
Several pilots who were listening to the Brisbane Centre frequency reported hearing a transmission of static at the approximate time of the collision with terrain.
Post impact actions
The pilot reported difficulty in releasing themselves from the restraint and exiting the inverted aircraft. After exiting the aircraft, they attempted to access the passenger through the rear doors but were unable to due to the presence of significant smoke and flame. The pilot then re‑entered the aircraft through the crew door and located the passenger who was still secured in their restraint. The pilot, with limited assistance from the semi‑conscious passenger, undid the restraint and proceeded to extract the passenger from the aircraft. Shortly after the pilot and passenger exited the aircraft, the pilot collapsed, and operator personnel arrived and moved them to a safe distance from the wreckage.
The passenger succumbed to their injuries at the accident site. The pilot suffered serious injuries and was airlifted from the site to East Kimberley Regional Airport for transfer to the Kununurra Hospital before being transferred to Darwin for further treatment.
Context
Aircraft Information
NPT was a Beechcraft B58, low-wing, twin engine aircraft (Figure 4). It was manufactured in the United States in 1996 and first registered in Australia in 2012. The aircraft was fitted with 2 Continental IO-550-C piston engines, driving 3‑blade constant‑speed propellers.
Figure 4: VH-NPT at the time it was purchased by the operator
Source: Operator
NPT was acquired by the operator in 2019. It was configured for charter operations with seating for up to 4 passengers in a club[5] configuration and seating for 2 pilots. The aircraft was configured with dual flight controls.
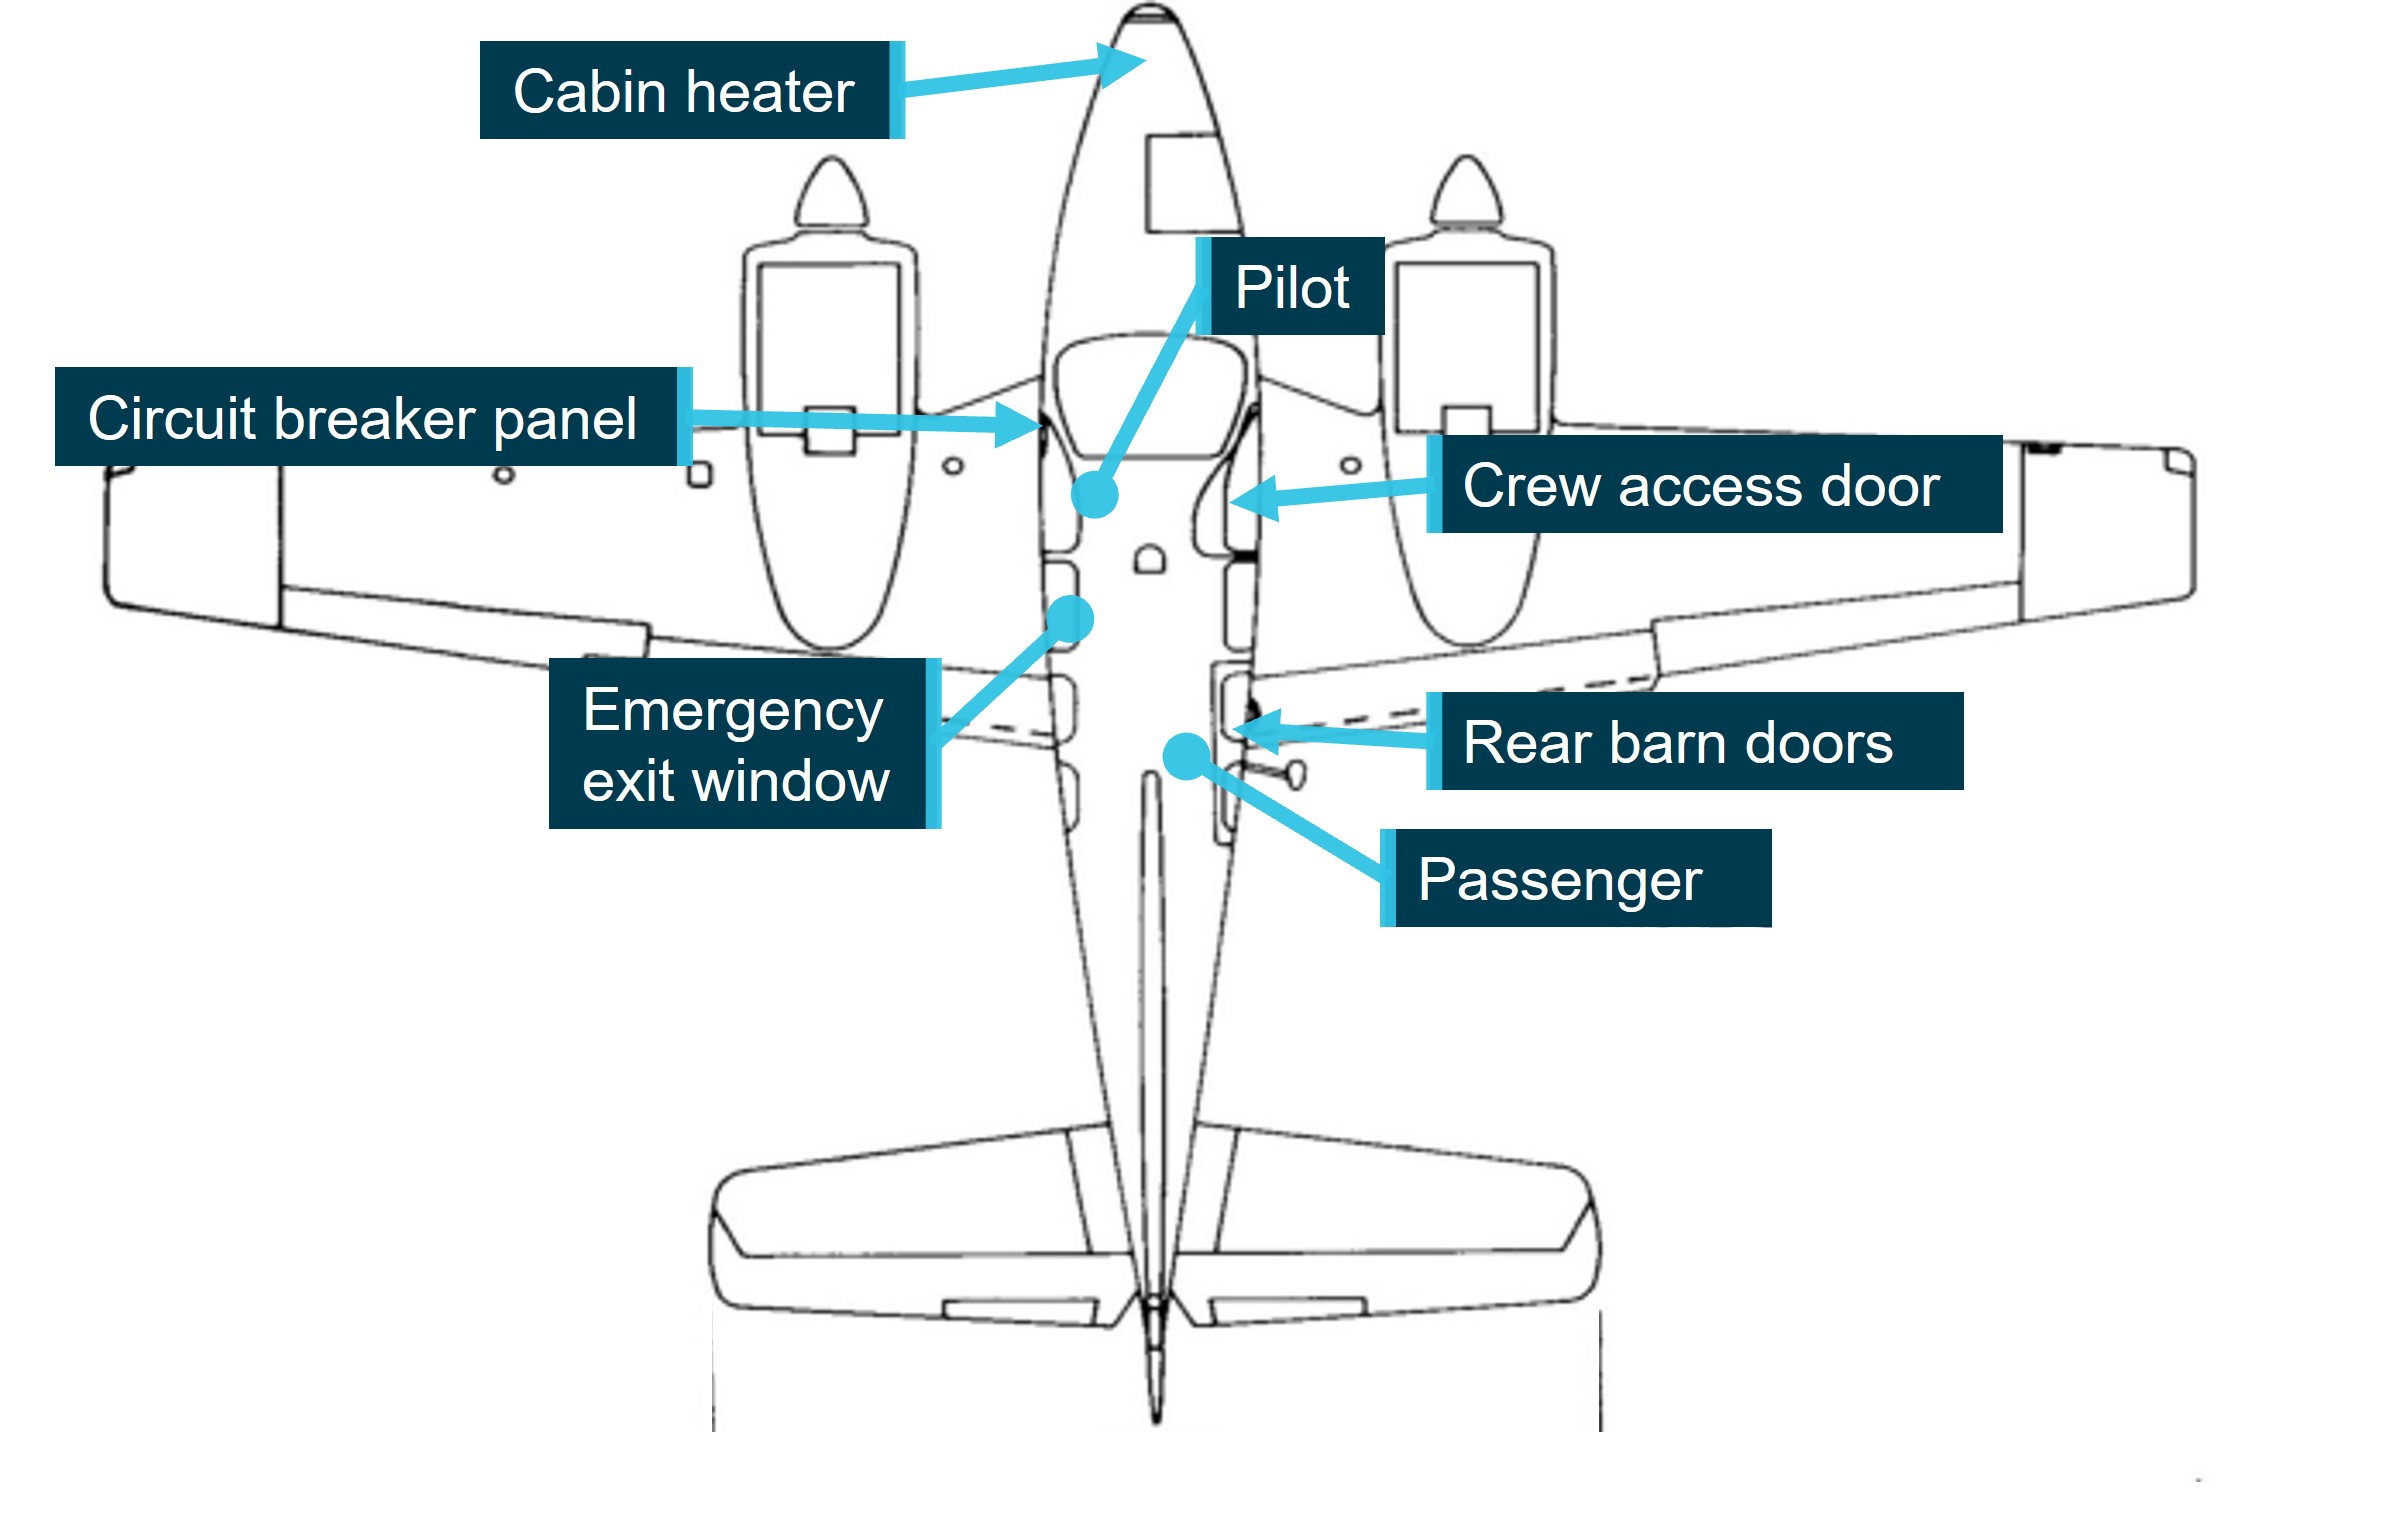
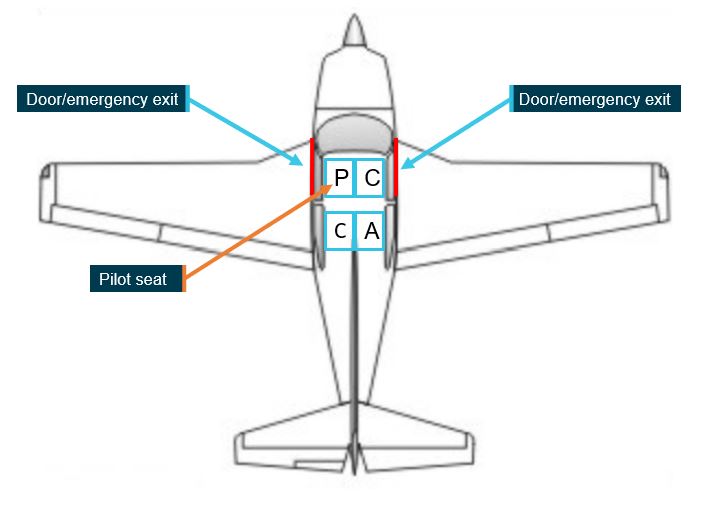
Access to the aircraft was through one of 2 doors, a crew door located on the front right of the aircraft next to the co-pilot’s seat, providing access to the front seats. Two rear or ‘barn doors’ on the right side of the aircraft provide access to the rear cabin for the loading of persons and freight (Figure 5). The aircraft was also fitted with an emergency exit window on the left side of the aircraft next to the left rearward facing passenger seat. This window could be opened by a passenger in the event of an emergency. The pilot reported that instruction on its operation was included in the pre-flight briefing to the passenger.
Figure 5: Aircraft schematic identifying location of key elements
Source: Manufacturer annotated by the ATSB
Weight and balance
Prior to departure the pilot determined that the aircraft would be within weight and balance limitations for each leg of the flight using the operator’s approved spreadsheet for NPT. The ATSB obtained a copy of the approved spreadsheet for NPT and confirmed the pilot’s calculations. This assessment also indicated that for the legs of the flight that the passenger was onboard, the aircraft remained within balance limits irrespective of the seat occupied by the passenger.
Fire suppression
In accordance with the manufacturer’s requirements, NPT was fitted with a handheld portable 2 kg halon fire extinguisher for emergency use by the crew. The extinguisher was located centrally between the pilots’ seats and the rearward facing passenger seats. The extinguisher was inspected and reweighed as part of the last 100 hourly inspection in accordance with Civil Aviation Safety Authority requirements.
The pilot commented that, while they were able to access and utilise the extinguisher, its positioning made it more difficult to access in the event of an emergency than in other aircraft within the fleet.
Electrical system
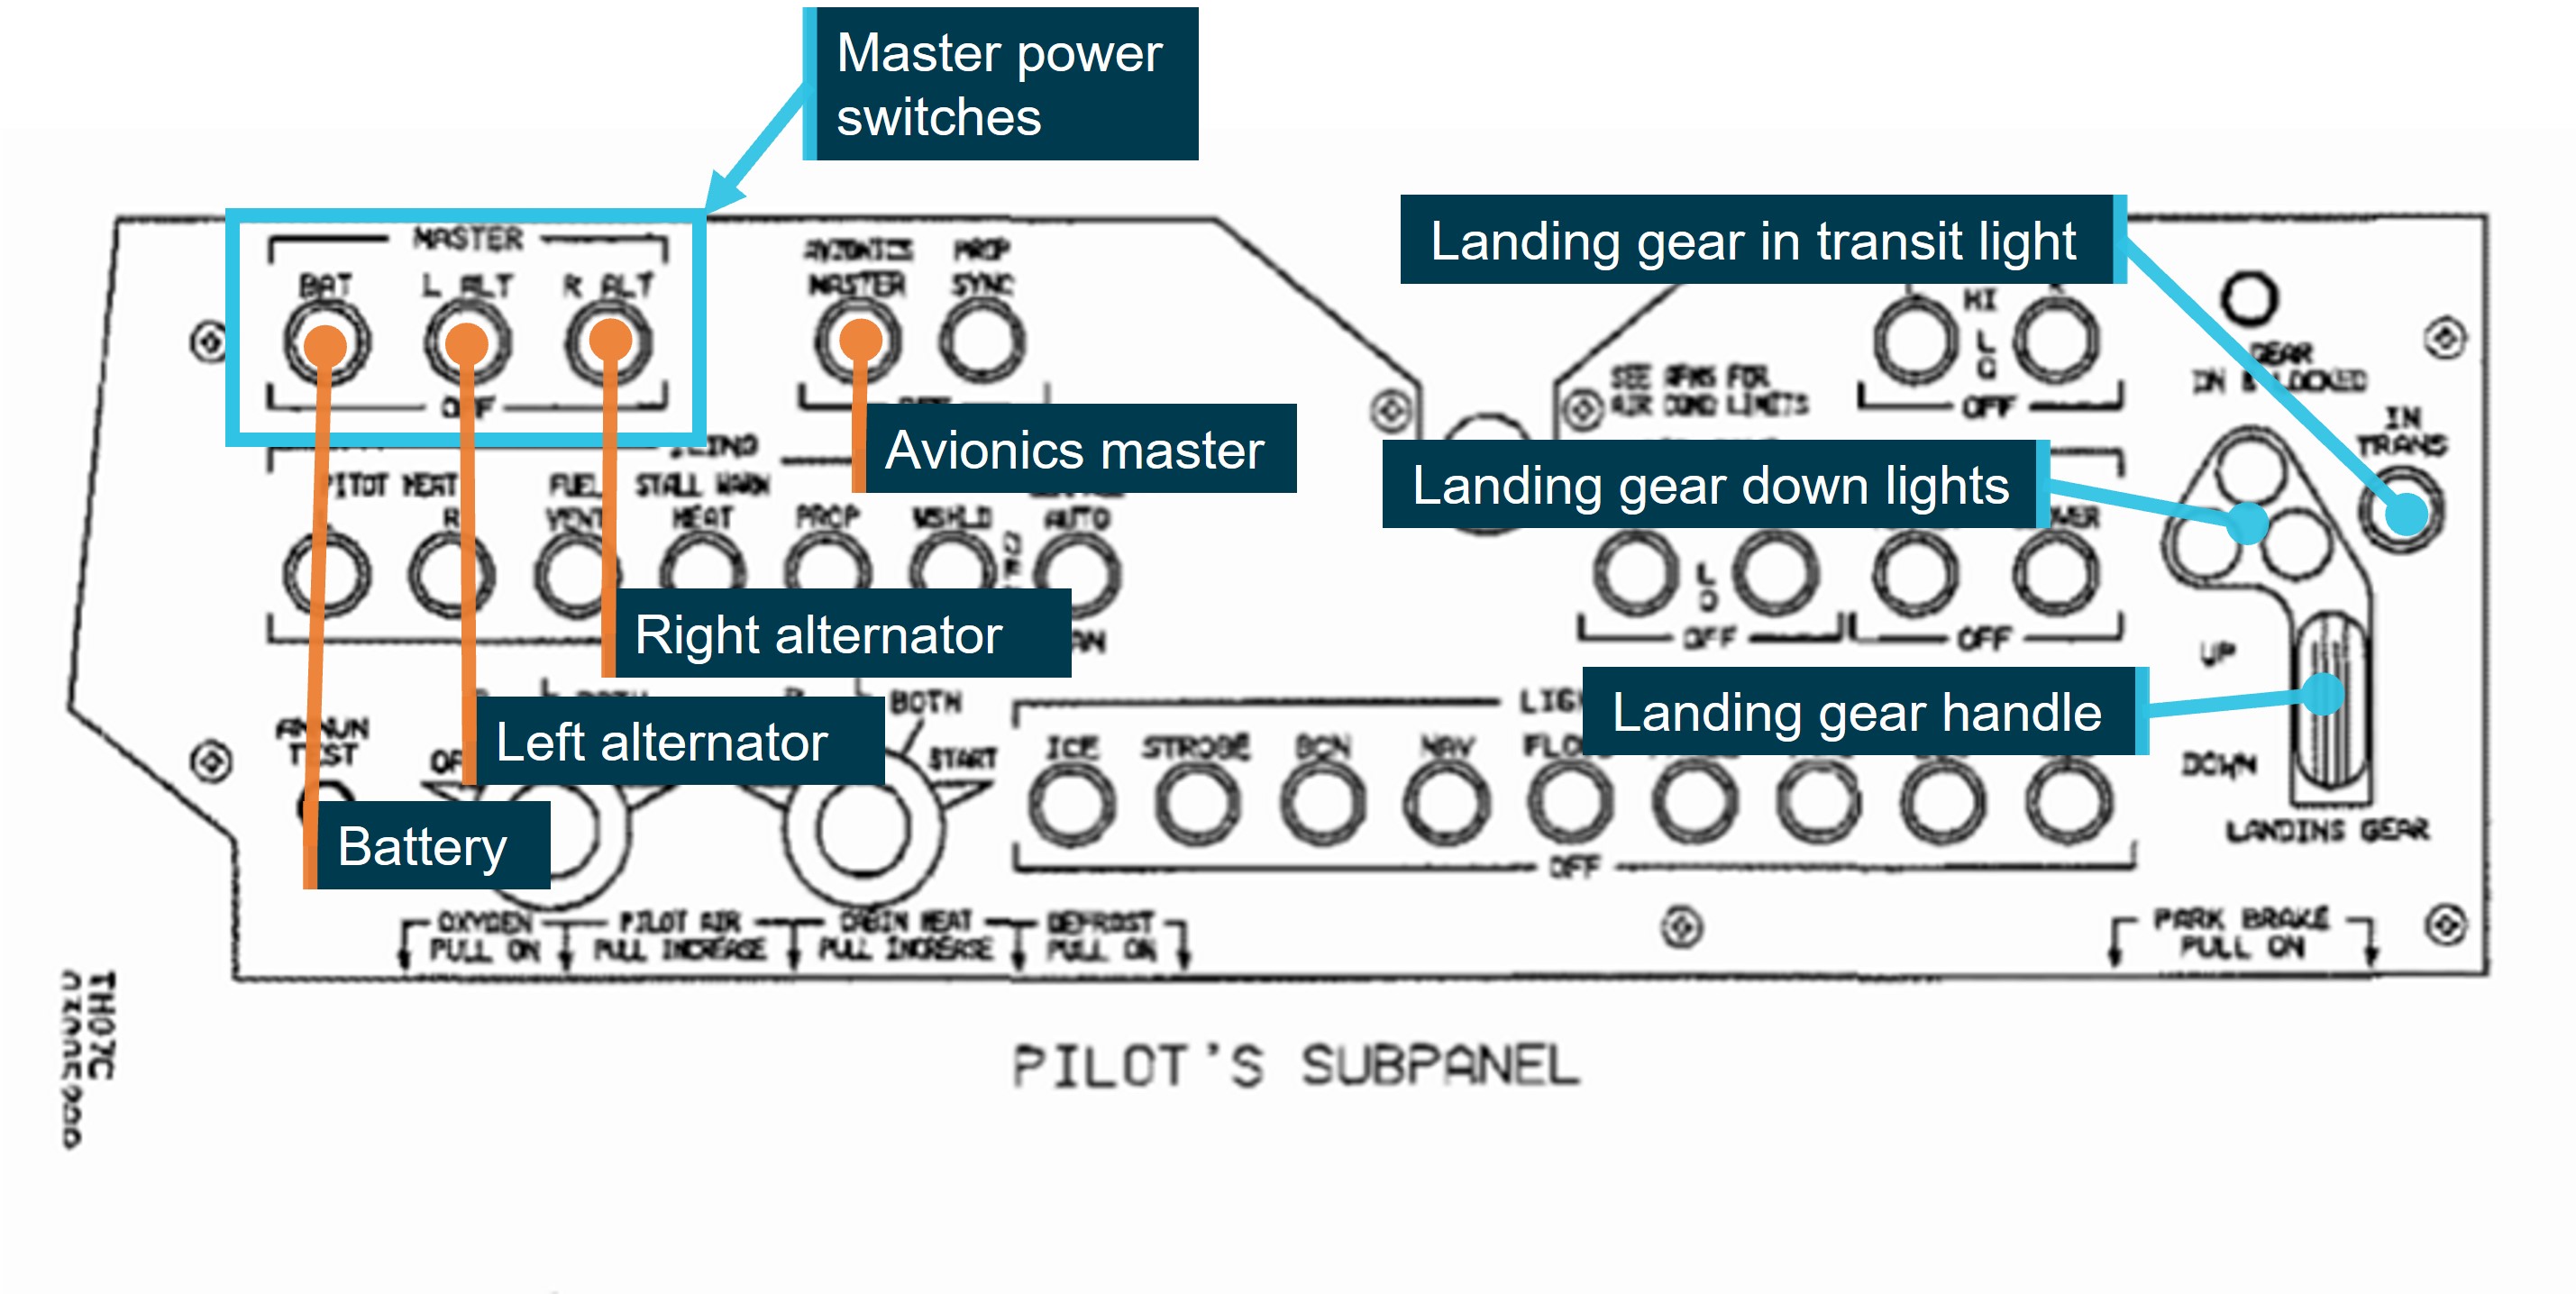
Aircraft power was supplied by a single battery and an alternator fitted to each of the aircraft’s 2 engines. These power sources could be connected and disconnected individually using 3 separate switches on the pilot’s sub‑panel labelled ‘MASTER’ (Figure 6). To protect the avionics from electrical damage when the master switches were being operated, a separate ‘AVIONICS MASTER’ switch (Figure 6) controlled power to these devices. The ‘AVIONICS MASTER’ was dependant on the ‘MASTER’ switches in the control hierarchy, meaning that if the ‘MASTER’ switches were off, the ‘AVIONICS MASTER’ was not able to be powered.
Figure 6: Schematic of the pilot’s subpanel showing master power and landing gear controls
Source: Manufacturer annotated by the ATSB
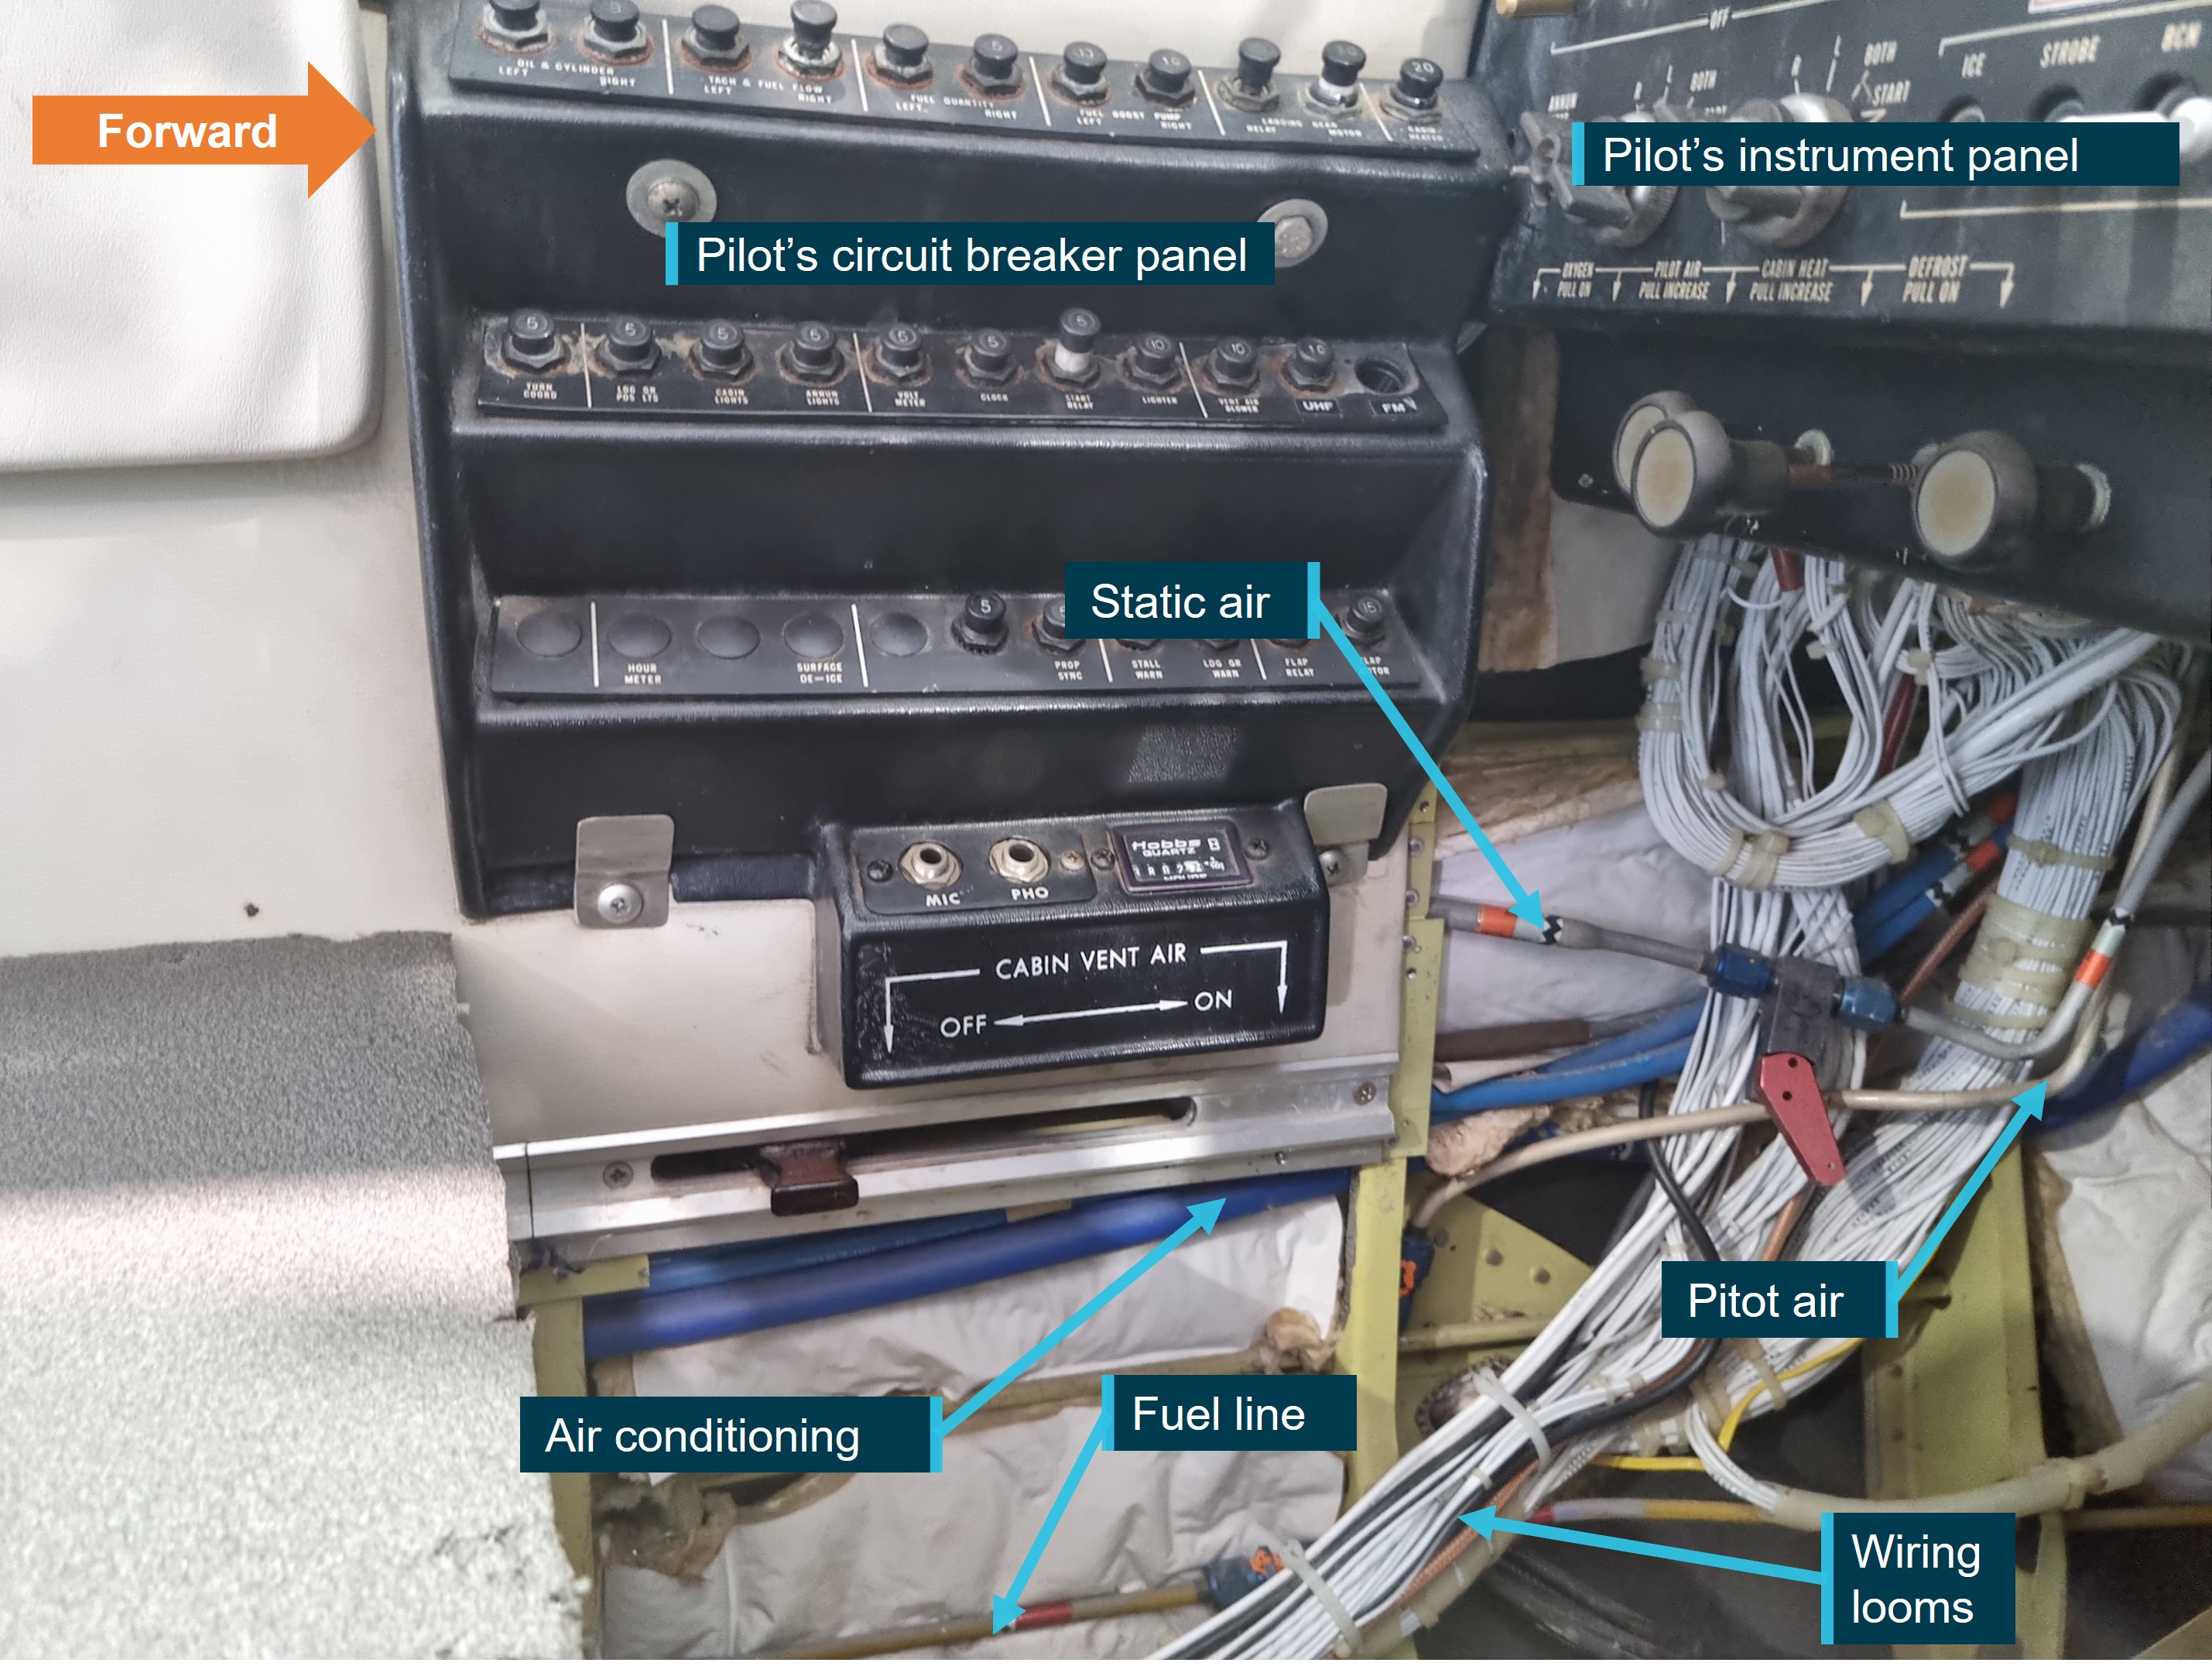
Electrical power was supplied to several systems including drive motors for the landing gear and flaps, aircraft lighting, avionics and communications. A circuit breaker panel on the pilot’s left side protects the circuits from overload and damage. Wiring was routed from the circuit breaker and instrument panels down along the left side of the aircraft in a series of looms. Figure 7 shows the area forward of the circuit breaker panel and below the pilot’s instrument panel in an exemplar aircraft.
Figure 7: Circuit breaker and instrument panel of an exemplar B58 showing the position of wiring looms.
Source: Operator annotated by the ATSB.
Based on the pilot’s report of the abnormal landing gear behaviour, the ATSB conducted a detailed examination of the system function. The landing gear system consists of:
a motor driving the gear between the extended and retracted positions
an indicating system that identifies to the pilot when the gear is retracted, extended or in transit
an aural alert that the gear is not extended if the aircraft is otherwise configured for landing.
Landing gear motor
The landing gear handle (Figure 6) acts as an electrical switch closing either the retract or extend landing gear motor circuit and powering the motor. Current flows through the switch and landing gear limit switches[6] to the motor relays. They are connected to the pilot’s circuit breaker panel by wiring on the left side of the aircraft and protected by a 5-amp circuit breaker. The relays operate a separate 30-amp circuit providing power directly to the landing gear motor. The switches and relays within the gear motor system provide power, with the motor constantly grounded. The landing gear motor is located below the floor of the aircraft between the crew and passenger seats.
Landing gear indication
The landing gear indication system consists of 4 lights, including one for each of the left, right and nose gears indicating they are in the down and locked position. A fourth light indicates that the gear is in transit. The lights are positioned above the gear handle on the instrument panel on the pilot’s subpanel assembly (Figure 6).
The lights are connected to down-lock and up-lock switches on each of the gear. The in-transit light is illuminated when either the down-lock or up-lock switches on any of the gear are not depressed. Once the down lock switches on each gear is closed, the light for that gear is switched on and once all 3 down lock switches are activated, the in-transit light switches off. These lights are connected to a 5-amp power supply and are switched on by grounding the circuit through these switches.
Landing gear warning
The landing gear warning system warns the pilot if the aircraft is incorrectly configured for landing due to the gear not being extended. The system consists of a warning horn connected to flap, throttle, and landing gear position switches. The horn will activate if the flaps are extended to full and the throttles are retarded while the landing gear is selected up.
The wiring for these systems, and several other electrical systems, are bundled together in the area where the pilot reported the fire started. The ATSB’s review of the aircraft electrical wiring schematics was not able to identify a single point of failure, either through a short between systems or to ground or an open circuit, which could have caused all 3 symptoms that the pilot reported. However, the bundling of multiple wires and the possibility of live circuits contacting one another meant that a multiple point failure in the landing gear, or within other electrical circuits, leading to the symptoms the pilot reported was possible.
Other electrical anomalies
After the pilot selected the landing gear to the down position and the fire commenced, the pilot reported switching off the aircraft’s electrical power and that the aircraft’s avionics screens went black. Spider Tracks data (see the section titled Recorded data) ceased shortly after this, however the aircraft’s ADS-B transponder continued to transmit (see the section titled Recorded data) until just before the aircraft collided with terrain. Following the PAN-PAN, no radio transmissions from the aircraft were recorded on the Brisbane Centre frequency. However, multiple pilots operating in the area at the time reported significant static on this frequency at approximately the time the aircraft collided with terrain, possibly indicating that NPT’s radio was powered.
Cabin heater
The B58 is fitted with a fuel‑burning cabin heater in the nose of the aircraft (Figure 5). Maintenance records indicated that the heater was infrequently used, and the pilot advised that the heater was not utilised during the accident flight. In the 12 months leading up to the most recent 100 hourly inspection the heater had been used for 102.5 of the aircraft’s accumulated 1,077 hours, of which only 3.3 had been accrued in the last 6 months. The heater’s hour count following the 100 hourly inspection was unable to be determined due to the post impact fire.
The heater is supplied with fuel via a direct line from the left-wing leading-edge fuel tank. The fuel line is attached to the tank at the wing root and traverses internally along the lower left fuselage. It passes through the aircraft cockpit below the pilot’s circuit breaker panel (Figure 6). The line then enters the aircraft’s nose-wheel bay and connects to the heater. The line fills with fuel as the tank is filled and will remain full of fuel at all normal flight attitudes. The line is secured at multiple locations with clamps to prevent damage from contact with the aircraft’s structure.
When the heater is running, fuel flows through the line at a rate of about 4 litres per hour.
Maintenance history
The last 100 hourly inspection was completed 9 days prior to the accident flight. Since that time, and prior to the accident flight, the aircraft had accrued 18.7 hours of flight time.
Concurrent with the 100 hourly inspection, additional maintenance tasks were carried out on NPT. One of these tasks was a repair to the leading-edge fuel tank in the aircraft’s left wing. A leak was identified during a post maintenance fuel leak check and traced to a gasket on the tank. Maintenance records indicated that the fuel bladder was manoeuvred to access and replace the leaking gasket. Records did not indicate if the line to the cabin heater was disconnected prior to the maintenance taking place. Following the repair to the gasket a further post maintenance leak check was carried out with nil defects identified. The aircraft manufacturer’s 100 hourly inspection required that the heater be inspected in accordance with the heater manufacturer’s manual. The manual required an operational check of the heater, including at least 2 operational cycles.
The ATSB reviewed the aircraft’s logbook and maintenance release, no references were identified to a fuel leak or a potential fuel smell in the cockpit between the time the 100 hourly was completed and the accident flight.
Restraints
NPT was fitted with 2 types of restraints, 4-point harnesses for the crew seats and 3-point harnesses for both the forward and rearward facing passenger seats in the main cabin. The 4‑point harnesses fitted to the crew seats were not original equipment and had been retrofitted to the aircraft prior to its purchase by the operator, replacing the existing 3-point harnesses. These restraints were in accordance with or exceeded regulatory requirements (see the section titled Survivability - Restraints).
Flammability resistance
The B58 was certified under Part 3 of the United States Civil Air Regulations as amended in 1956, which required that materials making up the cabin interior be ’flash resistant’, or ’flame resistant’ if the compartment could be used for smoking.
The type certificate data sheet for the B58 required placarding that the aircraft was non-smoking for serial numbers TH-2173 and later. The interior of NPT, being an earlier serial number, was required to meet the standard for a flame-resistant interior.
Flame resistant materials are required to resist flame advance of more than 4 inches per minute. Flash resistance required average flame advance to be less than 20 inches per minute.
These progression rates are tested under controlled conditions in accordance with FAA advisory circular 23-2A. The tests are conducted on the materials in isolation and do not account for accelerants being present.
Site and wreckage information
The initial collision point with terrain was approximately 45 m from the main wreckage location with the aircraft tracking approximately 117° and becoming inverted during the impact sequence.
Despite the aircraft being consumed by a post impact fire some of the aircraft’s contents, including several documents and personal effects were ejected during the impact sequence, leaving them largely unaffected.
Due to the severity of the post‑impact fire, the ATSB was not able to conduct a complete wreckage examination. However, there was evidence of engine rotation prior to the collision with terrain and no evidence found of pre-existing defects in the engines or flight control components that could have contributed to the accident. The landing gear was observed in the stowed position and no landing gear impact marks were visible at the accident site.
Aircraft windscreen
During the impact sequence the aircraft’s windscreen fractured and was liberated from the fuselage in multiple pieces. Some of these pieces, were clear of the post‑impact fire and were located nearby in long grass with their internal surfaces facing down.
The ATSB was able to reassemble almost the entire windscreen on-site (Figure 8). Once reassembled a soot trail was visible on the internal surface of the left side of the windscreen. The trail, emanating from the bottom of the windscreen, was approximately 34 centimetres from the left edge. The soot was of sufficient thickness that a clearly visible trail was able to be wiped into it. At the point where the soot trail initiated, the windscreen material exhibited a different failure mode, likely associated with significant heat.
Due to environmental conditions on-site the soot trail was not easily visible in captured image. The outside surface of the windscreen was subsequently marked on site with yellow paint marker identifying lateral extremities of the soot trail.
Source: ATSB
The upper, aft corner of the pilot’s storm window surround (Figure 9) was located with the outer surface down, closer to the post‑impact fire than the windscreen. Soot was located on both sides with the external surface, consistent with soot being drawn out of the window by the airflow.
Figure 9: Smoke and soot indications on window surfaces adjoining the pilots storm window
Source: ATSB
Flaps
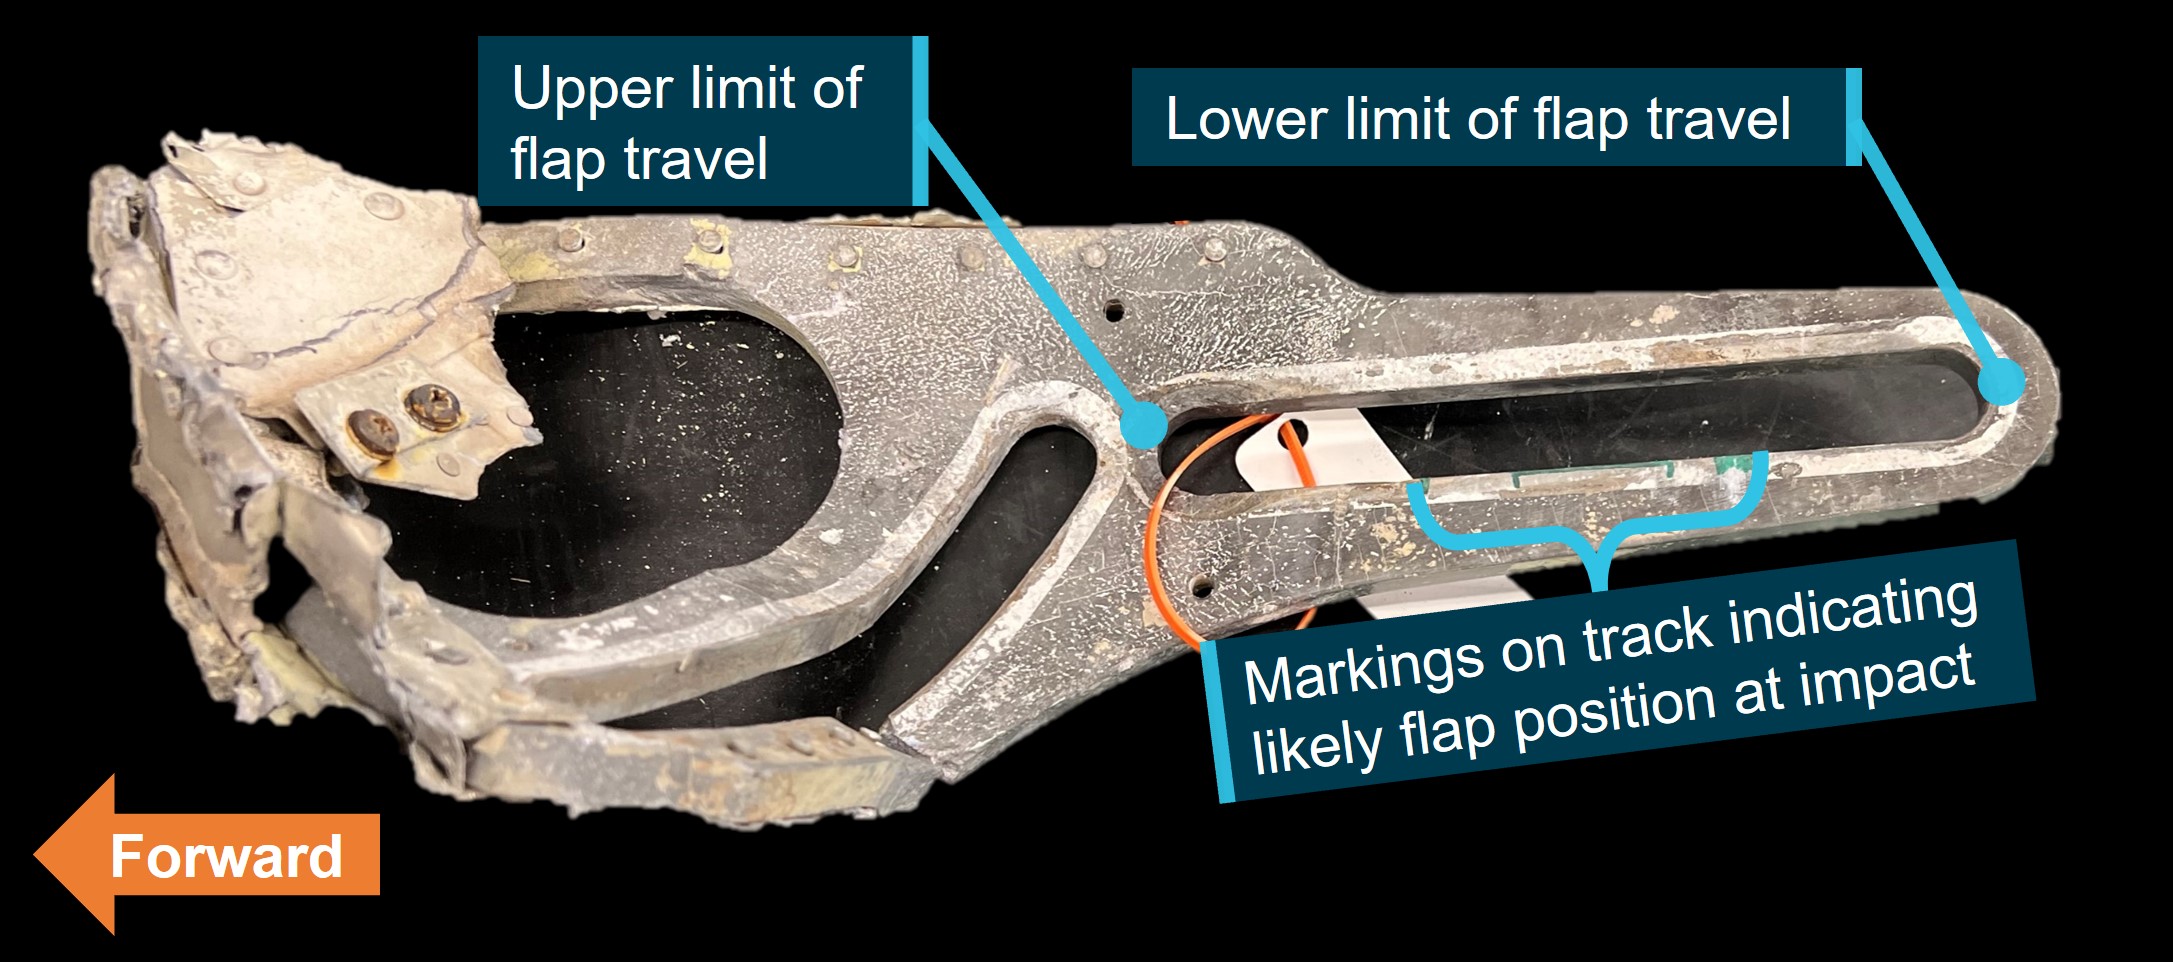
Due to fire damage to the flap actuators, the specific position of the flaps at impact was unable to be determined. The aircraft’s flap tracks were recovered for further examination at the ATSB’s technical facilities in Canberra. Impact markings on the flap tracks indicated that the flaps were likely extended to the first of the 2 flap positions (15°) at the time of impact (Figure 10). This corresponded with both the pilot’s report of having extended the flaps one position prior to activating the landing gear and the operator’s procedures that required first stage flap extension as part of the setup of the aircraft for the approach.
Figure 10: Left inboard flap track with markings indicating likely flap position at impact
Source: ATSB
Possible tree strike
In response to witness reports that the aircraft skimmed trees prior to the ground collision, the operator conducted an airborne search on the western side of the Ord River. This search identified a grouping of 4 trees in the approach to runway 12 that had damage consistent with aircraft contact.
The trees were approximately 500 m west of the river and 60 m north of the extended runway 12 centreline (Figure 11). Their position was consistent with the aircraft’s approach path, and were close to the lowest point in the aircraft’s flight path data on the western side of the Ord River. Tree damage was between 15 and 20 ft above ground level and the direction of the breaks and fallen limbs were consistent with the aircraft’s direction of travel.
Figure 11: Possible tree strike location
Source: Google Earth, Operator, AvPlan and Airservices Australia, annotated by the ATSB
Other than evidence of a collision with a number of small trees at the accident site, no additional tree strikes were identified, and no evidence of a foliage strike was located on the wreckage, however the significant fire damage prevented a detailed examination.
Pilot information
The pilot held a current Commercial Pilot License (Aeroplane), with their last flight review conducted in December 2021. They also held a:
Class 1 aviation medical certificate, valid until January 2023
multi engine aircraft instrument rating with retractable undercarriage and manual propellor pitch control endorsements.
Prior to the accident flight, the pilot had accumulated approximately 2,482 hours of aeronautical experience, of which just over 120 hours were in command of the B58. The pilot had completed their most recent operational proficiency check on 9 January 2022 and a line check in the B58 was carried out on 25 January 2022.
Meteorological information
An aerodrome meteorological report (METAR[7]) was issued by the automatic weather station at East Kimberley Regional Airport approximately 7 minutes before the accident. The report showed fine weather, with winds from the north at 2 kt, visibility greater than 10 km and nil cloud detected.
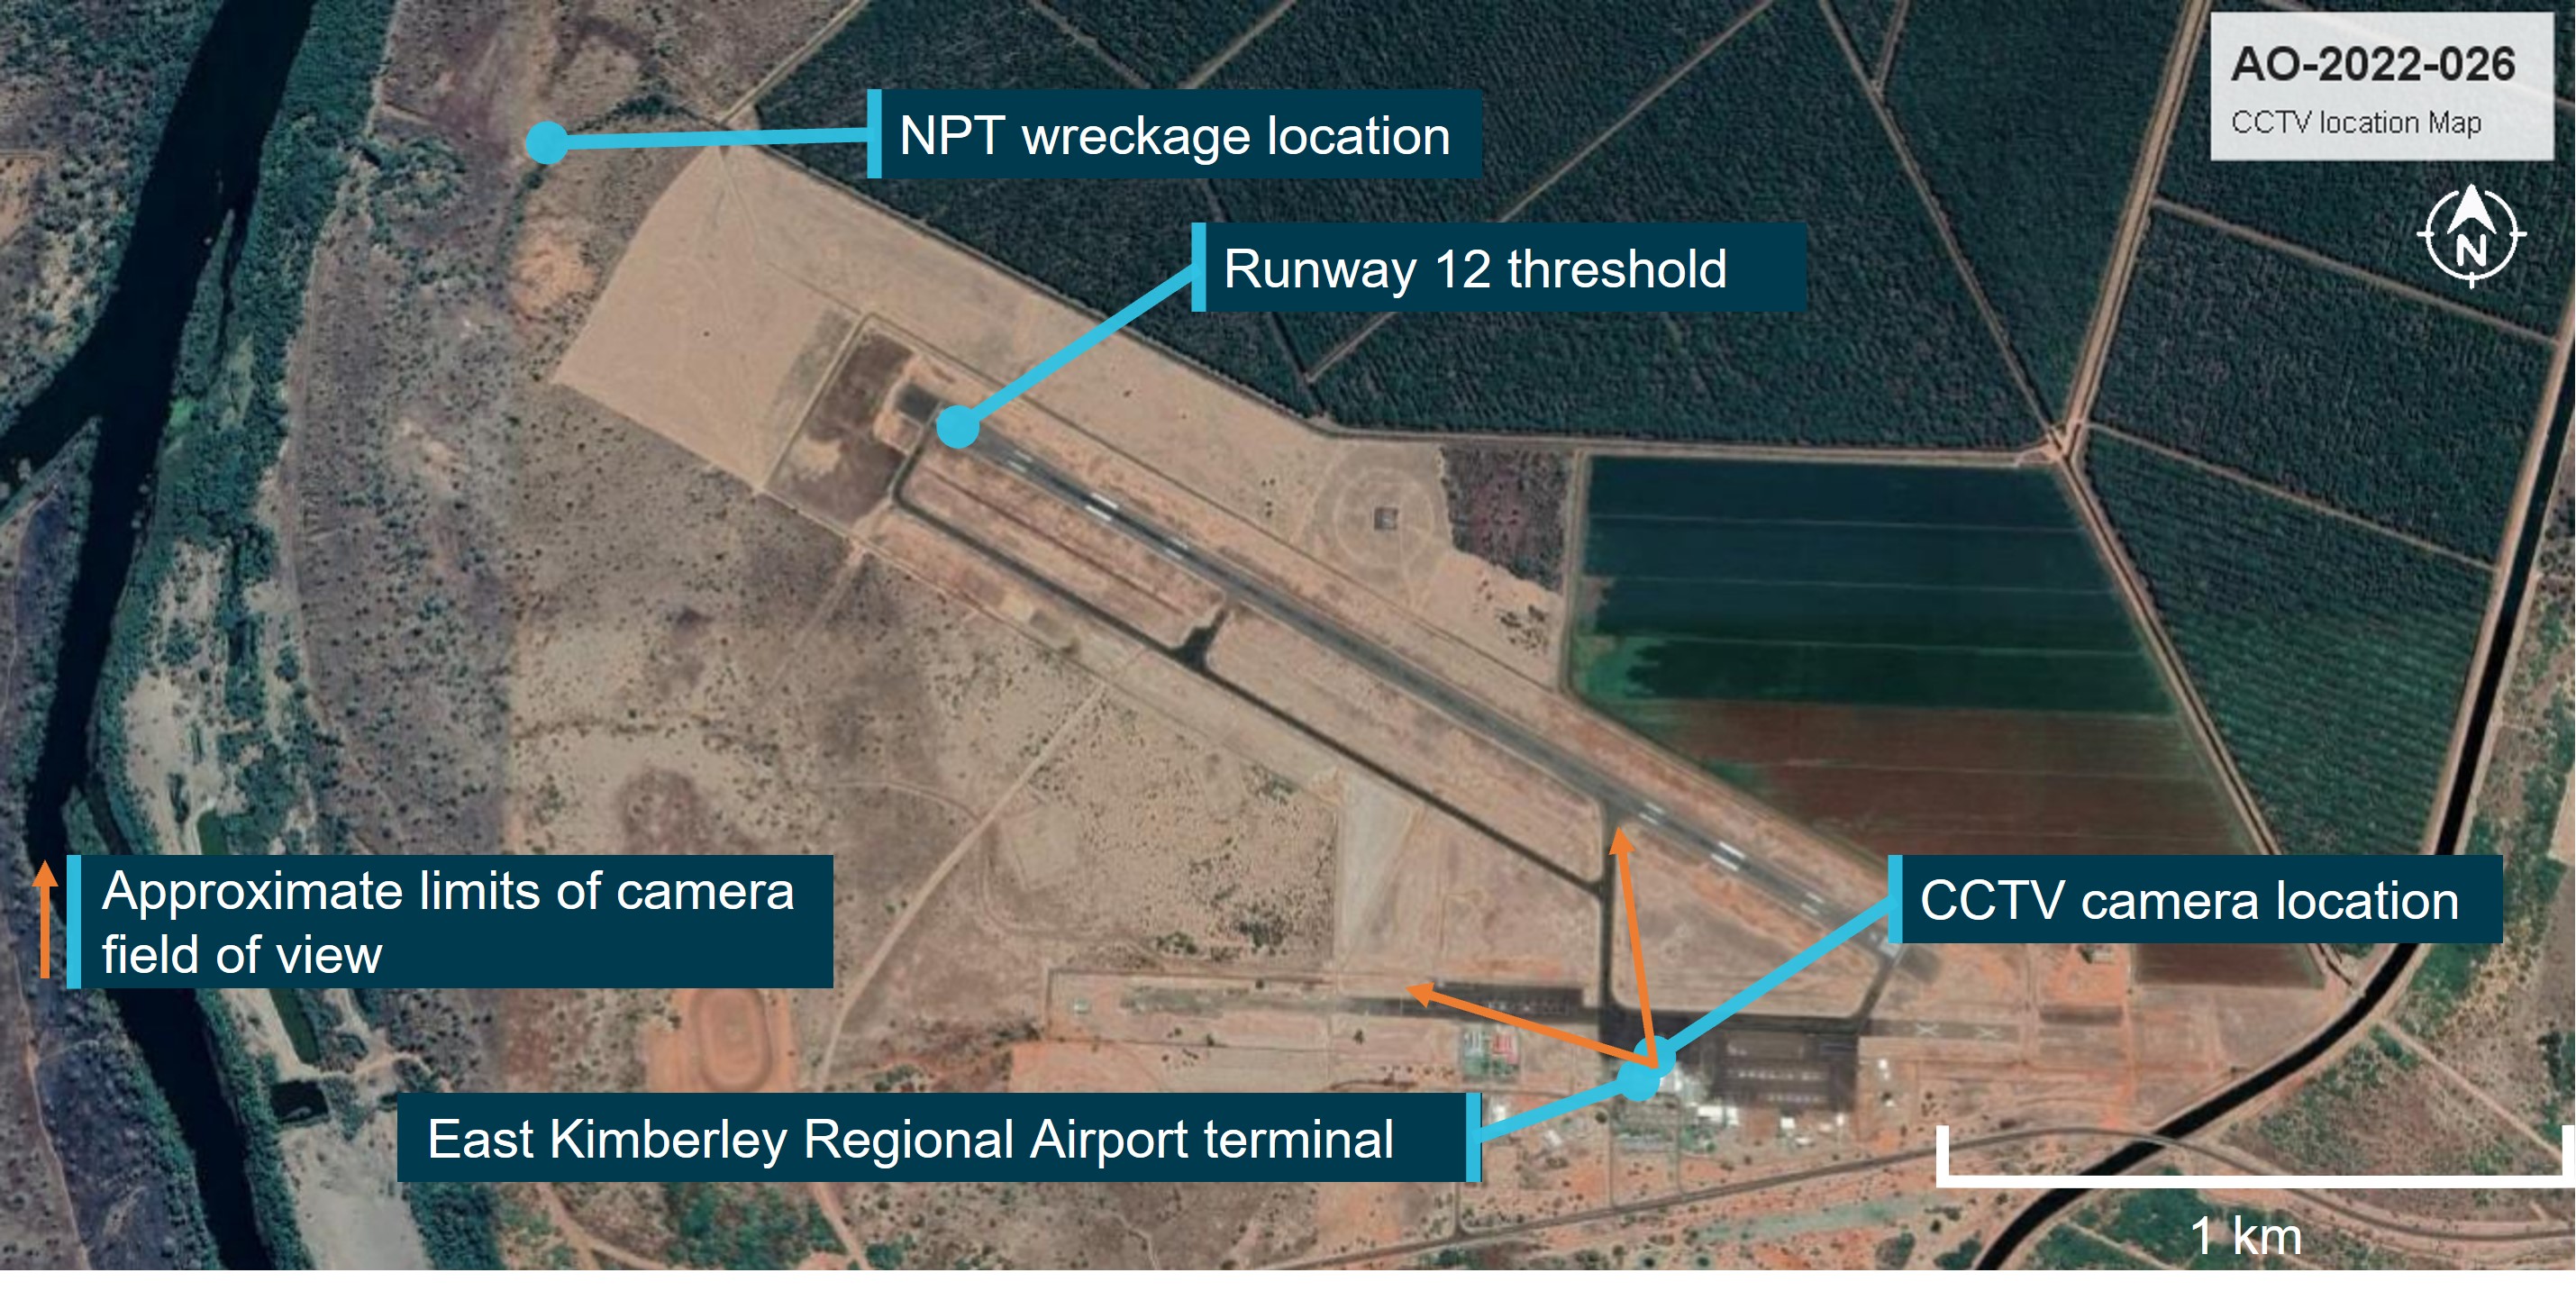
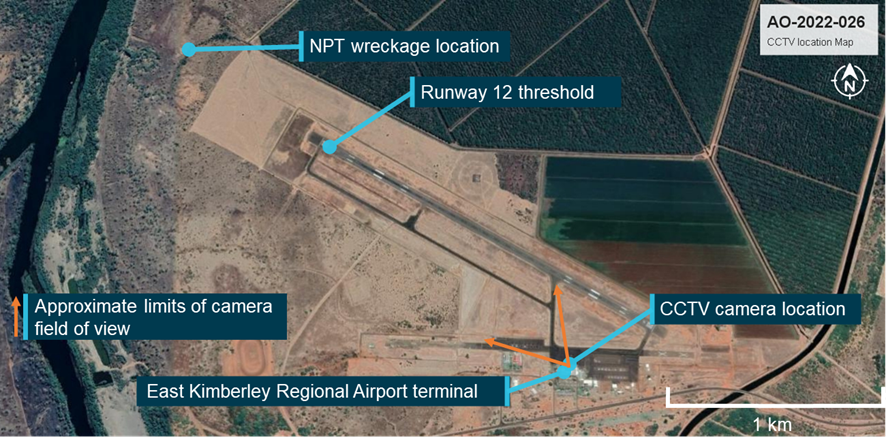
The ATSB also reviewed CCTV footage from the East Kimberley Regional Airport, which captured the smoke plume from the accident. Figure 12 shows the location of a camera covering the regular public transport apron. The camera image showed a smoke plume rising near-vertically from the accident site approximately 3 minutes after the accident indicating little to no wind immediately after the accident, consistent with the METAR.
Figure 12: Location of CCTV camera
Source: Google Earth annotated by the ATSB
Survivability
In reviewing the survivability aspects of this accident, the ATSB sought expert guidance from the Royal Australian Air Force Institute of Aviation Medicine (IAM). Their report formed the basis of the following section.
Restraints
Injuries to aircraft occupants arising from traumatic contact with aircraft structure occur at least 5 times more often than acceleration‑related injury. Within small aircraft that have confined interiors, lap belts and upper torso restraints are critical to crash survivability for both crew and passengers. The restraint of the upper body serves 2 purposes:
reducing the likelihood of impacting structures by minimising body flailing
distributing forces more widely across the body, making them more likely to be survivable.
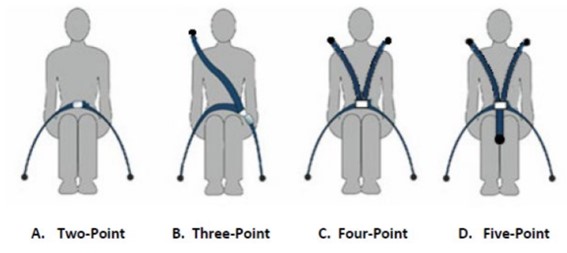
Upper torso restraints can be provided with a single shoulder strap, like that used in a car seatbelt or 2 straps, one over each shoulder. Figure 13, below, shows the difference between 2-, 3- and 4-point restraints. The image also shows a 5-point restraint that has a crotch strap which provides additional protection for the wearer, preventing them from ‘submarining’ or sliding under the lap portion of the restraint.
Figure 13: Aircraft restraint types.
Source: United States Department of the Interior via IAM
Both 3- and 4-point harnesses restrain the upper torso. However, the 3-point only provides lateral restraint in one direction, if the person flails to the unrestrained side they may come out of the shoulder strap rendering it ineffective. Additionally, with only one strap over the torso, the 3‑point restraint has a smaller surface area than the 4-point, increasing the force exerted to the restrained area on the wearer.
In accordance with Civil Aviation Safety Regulation (CASR) 90.105 the flight crew seats must be fitted with a restraint that consists of a lap belt and at least one shoulder strap. Requirements for occupant restraints are outlined in CASR 90.110 and require all occupant seats for aircraft with less than 10 seats and manufactured after 13 December 1986 to be fitted with an approved seat belt and shoulder harness.
Seating
It is generally accepted that in the event of a frontal impact a rearward facing seat will increase survivability in two ways.
Spreading the impact force over the entire surface of the back rather than specific areas where a restraint is positioned.
Limiting the movement of the head through flexion and extension of the neck, provided the seat is fitted with an appropriately positioned headrest.
There is no Australian regulatory requirement for the use of rearward facing seats. Their use is subject to availability and based on a range of operational considerations. These include weight and balance, emergency egress, other payload items (cargo), company procedure and passenger and pilot comfort. The ATSB recovered all seat frames from the aircraft wreckage. However, due to the severity of the post‑impact fire the ATSB was not able to conduct a detailed assessment and determine their effectiveness in attenuating impact forces and any subsequent effect on survivability.
Injuries
IAM reviewed the hospital and post-mortem records of the pilot and passenger respectively and provided a summary of their injuries. Both the passenger and the pilot received injuries attributable to both the fire and the collision with terrain. While there were some similarities in the injury profiles, the passenger’s injuries included more severe burns and trauma to the neck and chest, consistent with a single shoulder restraint and flailing within the aircraft, that the pilot did not suffer.
Recorded data
Spider Tracks
The last non-SOS Spider Tracks data point, available to the nearest minute was recorded at 0835. Immediately after this, still at 0835, two ’SOS Opened’ data points were recorded, indicating that the SOS function has been activated. No further data was received by the operator.
The SOS function increases the frequency of the data transmissions to 10-15 second intervals rather than the standard 2 minutes. Data from the pilot’s electronic flight bag (EFB) application indicated that the aircraft collided with terrain at 0837. If the Spider Tracks unit had remained powered after the 2 SOS data points at least 8 further transmissions should have been received. If the activation of the SOS function had not triggered the increase in data frequency, then one more point may have been received at 0837, depending on the exact time that the 0835 data point was transmitted.
The operator advised that the Spider Tracks unit was connected to aircraft power and the loss of signal from the Spider Tracks indicated a loss of electrical power to the aircraft.
Electronic flight bag
The operator utilised the AvPlan EFB application for pilots to undertake flight planning tasks, access electronic information, such as charts or relevant documentation and depending on the settings, display nearby traffic. The application can also record aircraft position information at 5‑second intervals. The pilot of NPT had a device with the application installed and active for the flight, for which the ATSB received data. This provided multiple flight parameters including ground speed and tracking details for the aircraft from the time of take-off until it collided with terrain.
The device was powered by an internal battery. However, it could be connected to aircraft power to keep the battery charged. The loss of aircraft power would not reduce the functionality of the device or effect the data recorded while the battery maintained its charge.
ADS-B
The aircraft was fitted with a transponder that broadcast ADS-B[8] data to ground stations and nearby aircraft fitted with ADS-B IN. The ATSB retrieved the data transmitted by this unit from ground stations operated by both Airservices Australia and other third-party receivers, including one at the East Kimberly Regional Airport.
Data obtained from the receivers operated by Airservices Australia and several third-party receivers, recorded the aircraft’s location from Broome until 0835 when the aircraft started the approach to runway 12 at East Kimberley Regional Airport. The signal was then lost, likely due to the aircraft’s descent taking it below the coverage altitude for these receivers.
An ADS-B receiver at the East Kimberley Regional Airport received data from the aircraft between 0834 and 0837. This recorded the aircraft passing KNXWF and commencing the approach to the East Kimberley Regional Airport. The final position report was received at 0836:43. Between 0836:43 and 0837:12 eight more data packets were received containing NPT’s mode S transponder code, however position information was not included.
The aircraft was fitted with a GTX33 ADS-B transponder unit, which was not equipped with an internal backup battery.
Related occurrences
The ATSB identified one occurrence in Australia and 3 in the United States that had similarities to this accident. These 4 occurrences involve in-flight fires accelerated by combustible hydrocarbons that were initiated by damaged electrical wiring. Each of these fires were different, with 2 relating to direct feeding fuel and oil gauges (which NPT was not fitted with), one was an engine fire, and one was a cockpit fire that was controllable. While different in detail, they all demonstrate the risks when electrical wiring and combustible hydrocarbons such as fuel and oil are in proximity.
On 26 February 2014 at about 1645 local time, a Beech 58 aircraft, registered VH‑SBS, departed Darwin for Gove, Northern Territory, on a private ferry flight with a supervising pilot and pilot in‑command-under-supervision (ICUS) on board.
At about 1815, the pilot flying ICUS saw smoke and flames by their left leg adjacent to the circuit breaker panel and immediately switched off the electrical master switch. The supervising pilot seated in the right seat took control of the aircraft and commenced an immediate descent. The pilot ICUS retrieved the fire extinguisher from underneath their seat and extinguished the fire.
An engineering inspection found electrical wiring penetrated through the heater supply fuel line causing it to arc and burn a hole in the fuel line. The wires had been bundled together and were rubbing on the fuel line.
NTSB investigations
Between 1983 and 2022 the NTSB’s public database identified 7 investigations where an inflight fire or explosion was listed as a factor. Of these, 3 were identified to be of particular relevance and are summarised below.
MIA00FA221
On 17 July 2000, approximately 7 minutes after departing Memphis Tennessee, the pilot of a B58 aircraft registered N158MT, serial number TH-1186, contacted ATC reporting that they had an electrical fire and were going to switch off the master. Following two further communications with ATC the aircraft collided with water at Arkabutla Lake. Witnesses reported seeing a ’vapor trail’ or ’dust’ coming from the aircraft. The pilot was fatally injured, and the aircraft was destroyed.
The NTSB investigation identified that the fire was likely the result of arcing of an electrical wire behind the pilot’s instrument panel and associated heat‑related cracking to fuel and oil lines that feed direct reading pressure gauges for fuel and oil pressure in the cockpit. The investigation also identified that the pilot had not switched off the engine alternator switches in accordance with the electrical smoke and fire emergency checklist.
SEA02FA023
During take-off, on 2 January 2002, the pilot of a B58 aircraft registered N132Z, serial number TJ‑284, identified a fire in the aircraft’s left engine. The pilot reduced power and landed the aircraft on the remaining runway. The pilot and the passenger evacuated the aircraft, which sustained substantial damage.
Further inspection identified that an improper clearance had allowed an alternator wire to chafe against a pneumatic line in the engine bay. The exposed wire subsequently arced to the aluminium line igniting fuel vapor. The most probable cause of the accumulated fuel vapor was from a fuel cell leak that had previously been repaired.
ERA11FA312
On 25 May 2011, a B58 aircraft, registered N77AR, serial number TH-757, with a pilot and 3 passengers on board was conducting a flight from Atlanta, Georgia to Hazard, Kentucky. At 1612 local time the pilot contacted ATC to advise they were declaring an emergency due to a fire on board. No further radio transmissions were received. ATC recorded 7 further transponder and 2 primary radar returns. Several witnesses observed the aircraft in its final stages of flight before it collided with terrain at approximately 1613 local time. The 4 occupants were fatally injured, and the aircraft was consumed by a post‑impact fire.
The NTSB investigation identified that an in-flight fire likely initiated in the right front cockpit area forward of the instrument panel and below the glare shield. While the NTSB was unable to conclusively determine the origin of the fire, their analysis notes that the speed of the fire’s advance was consistent with a fuel fed fire. The analysis also identified that the area where the fire was believed to have initiated was an area that is near the direct‑reading oil pressure gauges.
This report noted that B58 and 58A models with serial number TH-001 through TH-1193 were fitted with direct‑reading fuel flow and pressure indicators in the cockpit. Direct‑reading pressure indicators use a direct line from the engine to the cockpit for presentation of engine fuel pressure. The report noted that aircraft with serial number TH-1194 and later (NPT serial number TH-1769) were fitted with remote fuel flow indicators, removing the need for fuel lines to go directly to the cockpit.
Safety analysis
Introduction
At 0834 local time on 16 April 2022, the pilot of B58 Baron aircraft registered VH-NPT commenced a straight in approach to runway 12 at the East Kimberley Regional Airport at Kununurra. During the approach the pilot declared a PAN-PAN to air traffic control reporting smoke and suspected fire in the aircraft’s cockpit.
The pilot continued the approach, diverging from the runway centreline track as they crossed the Ord River. The aircraft collided with terrain on the eastern side of the Ord River approximately 800 m from the runway 12 threshold. The passenger sustained fatal injuries and the pilot sustained serious injuries.
The following analysis will examine the in-flight fire, looking at the sources of initiation and acceleration, the pilot’s loss of visual cues and factors that affected survivability.
In-flight fire
The pilot reported that smoke and subsequently flame emerged from below the left side of the instrument panel, below and forward of the circuit breaker panel. The pilot attempted to extinguish the fire with a portable handheld fire extinguisher. The extinguisher suppressed the fire, however once removed, the fire returned vigorously.
Within 90 seconds of the pilot declaring the PAN-PAN, the aircraft had collided with terrain. The pilot sustained serious burns to their left side and the pilot and passenger sustained fire‑related respiratory injuries.
Materials used in the interior trim of NPT were required to be flame-resistant. The fire progressed at a speed greater than what would be expected of flame-resistant materials, consistent with the fire being fuelled by an accelerant.
Acceleration
Several lines and multiple looms of electrical wiring pass through the area where the pilot reported that the fire initiated. The lines contain pitot and static air for instruments, air conditioning system gasses and the fuel line to the aircraft’s cabin heater. Of these, the fuel line to the cabin heater provided the only source for flammable liquid to accelerate the fire.
A breach in the fuel line forward of and below the pilot’s circuit breaker panel would allow fuel to enter the area behind the side wall trim panel, possibly being absorbed by the fibreglass insulation. This would provide a high energy acceleration source capable of overcoming the flammability resistance of the trim materials. A direct examination of the line, surrounding insultation and the trim panel was not possible due to the post impact fire. As a result, the integrity of the heater line was unable to be established.
Two possible scenarios were considered for when a breach in the fuel line may have occurred. The first was that the leak was initiated at the time the pilot detected the smoke. This would show significant similarity to the previous Australian occurrence (AO-2014-040) whereby the breach in the fuel line initiated and provided an accelerant for the fire. However, in the 2014 occurrence, the leak was small, and the fire was comparatively controllable. In the event of a larger breach, or the line fracturing, fuel would be liberated more quickly, decreasing the chances of controlling the fire effectively.
The second scenario considered fuel to have been leaking for some time prior to the initiation of the fire. If the fuel had been leaking previously this would allow accelerant to accumulate behind the trim panel and in the insulation. In this scenario a smaller leak could lead to the same issues controlling the fire as a larger breach occurring due to the accumulated fuel.
The pilot’s report of a ‘fuel like smell’ in the cockpit on the morning of the accident may support the line having been breached at some point prior to the aircraft taking off. However, the pilot reported that the smell was no longer present once airborne. Additionally, there was no reported evidence of fuel spillage on the ground and the aircraft had passed its fuel leak check following maintenance 18 flight hours earlier.
Due to the post impact fire damage the ATSB was unable to determine which of the 2 scenarios were more likely. However, once the fire was initiated, given its location, it would very likely have quickly burned through the heater line liberating fuel that remained in the line further accelerating the fire and contributing to its rapid return after the pilot suppressed it with the portable handheld fire extinguisher.
Initiation
The electrical burning smell reported by the pilot immediately before the smoke and subsequent flames were observed supports the fire being initiated by a fault in the electrical system. The pilot reported that all systems had been operating normally until the landing gear handle was selected to the down position. Following the operation of the landing gear handle the pilot reported that the landing gear did not extend and there were multiple abnormal landing gear system indications.
Wiring for both the indication and operational systems are contained in wiring looms that pass through the area where the pilot first observed the smoke. These looms run near one another and the aircraft structure. Undetected damage could occur to or within the wiring looms, providing an ignition source from chafing, overheating of wiring or wires shorting to another wire or the airframe. Due to the destruction of the aircraft wreckage the ATSB was not able to determine the exact sequence of events that led to the electrical fault, the initiation of the fire and the other electrical anomalies that occurred.
Despite that, previous occurrences in both Australia and the United States show the danger that damaged electrical wiring can pose in areas with flammable liquid lines.
Loss of visual cues
As the fire advanced it generated a large amount of heat and smoke in the cockpit as reported by the pilot and evidenced by the soot on the internal surfaces of the aircraft windscreen and the pilot’s storm window surround, both of which were separated from the post‑impact fire. The extent of this smoke likely prevented the pilot from being able to see visual cues external to the aircraft or to effectively use the instruments as a reference. That situation, combined with the direct heat of the fire, meant that the pilot was presented with significant difficulty retaining control of the aircraft.
Following the PAN PAN call the aircraft descended below the normal approach profile; however, the pilot was able to maintain the approach track until crossing the Ord River when the aircraft diverged to the left of the extended runway centreline. The pilot was subsequently able to regain the approach heading prior to the aircraft colliding with terrain.
Survivability
The survivability of the accident can be broken down into the environment within the aircraft prior to and after the collision and the impact forces related to the collision.
The fire generated significant heat and smoke in the aircraft’s cockpit. The reports of the pilot and the respiratory injuries to both occupants indicate that they were unable to effectively vent the smoke.
With the pilot able to self-extract after the collision, the passenger continued to be exposed to the environmental conditions within the aircraft until the pilot was able to re-enter the aircraft to extract them. This likely reduced the passenger’s chances of survival.
The pilot reported that they and the passenger were secured in their restraints at the time the aircraft collided with terrain. The pilot, in the left control seat was in a 4-point harness and the passenger, in the rear right seat, was in a 3-point harness. Generally, the 4-point harness improves survivability in 2 ways. Firstly, it better attenuates the impact forces, by spreading them more broadly over the body. Secondly, it secures the occupant more effectively laterally reducing flailing. This decreases the likelihood of injuries due to contact with obstructions or structure of the aircraft.
The primary difference in injuries between the 2 occupants of the aircraft was the chest and other trauma present in the passenger. This trauma was consistent with the differences between the use of a 3-point and 4-point restraint. The 3-point restraint did not distribute forces as evenly across the body and allowed significant multi-directional movement (flailing) inside the aircraft.
Based on advice from the manufacturer, operator and ATSB research a 4-point restraint is not available for the rear seat of B58 aircraft. However, this accident demonstrates the fitment of the 4-point harness to the crew seats, can improve survivability over the 3-point restraint that is required under the regulations.
Seating position
NPT was fitted with a club passenger seating configuration, with 2 forward facing and 2 rearward facing seats. As the pilot and passenger were seated in forward facing seats a comparison of injury profiles due to forward or rearward facing seats was not possible. However, the available literature supports that in the event of a frontal impact the rearward facing seat will provide better restraint of the occupant. By both spreading impact force more evenly over the whole back and reducing the potential for flailing by forcing the body into the seat.
For this flight, the ATSB reviewed the weight and balance documentation, determining that the aircraft remained within limits regardless of where the passenger or the cargo were positioned. Additionally, due to the size of the cabin, the passenger’s emergency egress route would not have been altered by changing positions.
Recognising that, when flight planning, pilots have many operational considerations when it comes to passenger positioning, in the event of a frontal impact, such as a collision with terrain, a rearward facing seat will generally better protect the occupant and increase their chances of survival.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the In-flight fire and collision with terrain involving Beechcraft B58 Baron, VH-NPT near East Kimberley Regional Airport, Kununurra, Western Australia on 16 April 2022.
Contributing factors
On approach to runway 12 at Kununurra, a fault associated with the landing gear electrical system likely ignited fuel from the cabin heater supply line, resulting in a significant and sustained cockpit fire.
Due to smoke in the cockpit, the pilot lost visual reference to both the instruments and outside environment. This, combined with the direct exposure to flames, led to a divergence from the extended runway centre line and the aircraft impacting terrain off the airfield.
Other findings
The 4-point harness that was installed for the pilot provided better restraint and attenuation of impact forces compared to the best available option of a 3-point restraint in the rear, leading to less severe impact related injuries.
The aircraft’s passenger cabin had a ‘club’ configuration with 2 forward and 2 rearward facing seats. Although not a requirement, positioning the passenger in rearward facing seat would have likely improved survivability from frontal impact‑related injuries.
Safety action
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future. The ATSB has so far been advised of the following proactive safety action in response to this occurrence.
Safety action by Aviair Pty Ltd
In response to this accident the operator reported that they
commenced a program to install 4-point restraints in the crew seats of all their B58 aircraft
installed an additional fire extinguisher in each of their B58 aircraft,
incorporated additional 100-hourly fuel line and wiring inspections in the vicinity of the heater fuel line and circuit breakers adjacent to the pilot’s seat.
Safety advisory notice to operators of B58 aircraft
In conjunction with the preliminary report released on 21 September 2022, the ATSB issued a Safety Advisory Notice to all B58 operators encouraging them to:
note the circumstances of this accident and previous ATSB investigation AO‑2014‑040
conduct a detailed examination of the wiring and fuel line on the left side of the aircraft forward of, and below, the pilot’s circuit breaker panel.
A copy of the Safety Advisory Notice can be found on the ATSB website here.
IAM Royal Australian Air Force Institute of Aviation Medicine
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot and operator
Civil Aviation Safety Authority
Western Australia Police Service
aircraft manufacturer
Airservices Australia
accident witnesses
CCTV footage and ADS-B data recorded at the East Kimberley Regional Airport
recorded data from AvPlan electronic flight bag application on the pilots iPad.
Royal Australian Air Force Institute of Aviation Medicine
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
pilot of the accident flight
operator
Civil Aviation Safety Authority
aircraft manufacturer
Royal Australian Air Force Institute of Aviation Medicine
Submissions were received from the:
pilot of the accident flight
operator
aircraft manufacturer
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] PAN-PAN: an internationally recognised radio call announcing an urgency condition which concerns the safety of an aircraft or its occupants but where the flight crew does not require immediate assistance.
[2] SOS function is an emergency transmission from the Spider Tracks unit that alerts predetermined personnel via text message that an aircraft is in distress and an emergency response is likely to be required.
[3] Spider Tracks is a subscription aircraft monitoring service that allows operators to track and monitor the location of aircraft at 2 minute intervals. The location is recorded and transmitted by a unit that is fitted to the aircraft. This unit also has ’Watch’ and ’SOS’ functions that allow the pilot to alert predetermined ground-based personnel of a situation requiring monitoring or an emergency situation.
[4] Storm Window is a small window inset in the pilot’s side window allowing ventilation, or visibility in the event it is lost through the forward windscreen
[5] Club configuration – the forward two seats in the rear passenger area are oriented to face the rear of the aircraft while the rear seats face forward.
[6] Landing gear limit switch prevents overdriving of the landing gear motor by disconnecting motor drive to the gear once it reaches the extended or retracted and locked positions.
[7] METAR - a routine aerodrome report of meteorological conditions at an aerodrome, normally issued on the hour and half-hour.
[8] Automatic Dependent Surveillance – Broadcast - A means by which aircraft, aerodrome vehicles and other objects can automatically transmit and/or receive data such as identification, position and additional data, as appropriate, in a broadcast mode via a data link
Preliminary report
Report release date: 21/09/2022
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
At 0613 Western Standard Time[1] on 16 April 2022, a Beechcraft B58 Baron (B58), registered VH‑NPT (NPT) and operated by Aviair Pty Ltd, departed Broome Airport, Western Australia, for a regular charter flight to several remote locations in northern Western Australia. The aircraft departed with the pilot, one passenger and 4 boxes of cargo on board. The flight was planned to transit through the East Kimberley Regional Airport at Kununurra (Figure 1) to refuel, then continue to Halls Creek where the passenger was to disembark, Fitzroy Crossing to unload cargo and then return to Broome via Derby.
Figure 1: Flight area
Source: Google Earth annotated by the ATSB
At 0749 WST the pilot called air traffic control (ATC) requesting traffic for a direct track to waypoint Kununurra Whiskey Foxtrot (KNXWF) for approach to runway 12 at Kununurra (Figure 2). At 0817 the pilot of NPT contacted ATC advising that they were leaving their cruising altitude of 9,000 ft on descent for Kununurra.
Figure 2: NPT flight path and Brisbane Centre radio calls
Source: Google Earth and AvPlan annotated by the ATSB
Seventeen minutes later NPT joined a straight in approach to runway 12. The pilot recalled slowing the aircraft, extending the first stage of flaps and attempting to extend the landing gear.
Upon selecting the landing gear handle, the gear down and locked indicators (3 green lights) illuminated immediately. The pilot reported that this was unusual, as normal operation required a few seconds for the landing gear to extend and the lights to illuminate. The pilot also recalled, co‑incident with the landing gear handle activation, that the landing gear warning horn erroneously activated, however no sound was heard from the landing gear motor and no decrease in aircraft performance was felt indicating gear extension. The pilot stated that these unusual indications were followed immediately by an electrical burning smell and smoke emerging from below the left side of the aircraft instrument panel, forward of the pilot’s circuit breaker panel.
About a minute later at 08:35:54 the pilot made a PAN PAN[2] call on the Brisbane Centre frequency advising of smoke and suspected fire in the cockpit. The pilot then activated the SOS[3] function on a dash mounted Spidertracks[4] unit. The pilot recalled switching off the electrical power to the aircraft and by that time flames were emanating from the same location as the previously‑observed smoke.
The pilot then expended the onboard fire extinguisher while continuing a straight in approach to runway 12 (Figure 4). However, the fire almost immediately returned, emanating from the same location, and creating significant smoke in the cockpit. The pilot reported that soon after this they lost visibility of both the instruments and the outside environment. In response, they opened the aircraft’s storm window[5] to attempt to clear the smoke and obtain a visual reference.
Figure 3: NPT approach to East Kimberley Regional Airport
Source: Google Earth, AvPlan and Airservices Australia annotated by the ATSB
Recorded flight data indicated that, at 0837, the aircraft started diverging significantly left of the extended runway centre line, crossing the Ord River at low level approximately 1.5km from the threshold of runway 12. The aircraft subsequently collided with terrain about 600m beyond the river and about 800m from the runway 12 threshold (Figure 4) and was consumed by a significant post‑impact fire.
The pilot sustained serious injuries but was able to extricate themselves and the passenger from the wreckage. The passenger later succumbed to their injuries.
Figure 4: NPT final approach and wreckage location
Source: Google Earth, AvPlan and Airservices Australia annotated by the ATSB
Context
Aircraft Information
NPT was a Beechcraft B58, low-wing, twin engine aircraft. It was manufactured in the United States in 1996 and first registered in Australia in 2012. The aircraft was fitted with 2 Continental IO-550-C piston engines driving 3 blade constant speed propellers.
NPT was acquired by the operator in 2019. It was configured for charter operations with rear club[6] seating for up to 4 passengers and front seating for 2 pilots. The aircraft was configured with dual cockpit controls.
The last 100 hourly inspection was completed 9 days prior to the accident flight. Since this time, and prior to the accident flight, the aircraft had accrued 18.7 hours of flight time.
The B58 is fitted with a fuel‑burning cabin heater in the nose of the aircraft. This heater is fed via a direct line from the left-wing leading-edge fuel tank. The fuel line traverses internally along the lower left fuselage entering the aircraft’s nose-wheel bay where the heater is located. Maintenance records indicated that the heater was infrequently used, and the pilot commented that the heater was not utilised during the accident flight.
Fire Suppression
NPT was fitted with a portable 2 kg halon fire extinguisher for emergency use by the crew. The extinguisher was located centrally between the pilots’ seats and the rearward facing passenger seats. The extinguisher was inspected and reweighed as part of the last 100 hourly inspection in accordance with Civil Aviation Safety Authority requirements.
Site and wreckage information
The initial impact point with terrain was approximately 45 m from the main wreckage location with the aircraft tracking approximately 117° and becoming inverted during the impact sequence.
Despite the aircraft being consumed by a post impact fire some of the aircraft’s contents, including several documents and personal effects were thrown clear during the impact sequence, leaving them largely unaffected.
Due to the severity of the post‑impact fire the ATSB was not able to conduct a complete wreckage examination. However, there was evidence of engine rotation prior to the impact and no evidence found of pre-existing defects in the engines or flight control components that could have contributed to the accident. The landing gear was observed in the stowed position and no landing gear impact marks were visible at the accident site.
Pilot Information
The pilot held a current Commercial Pilot License (Aeroplane) with their last flight review conducted in December 2021. They also held a:
class 1 aviation medical certificate, valid until January 2023
multi engine aircraft instrument rating with retractable undercarriage and manual propellor pitch control endorsements.
Prior to the accident flight, the pilot had accumulated approximately 2,482 hours of aeronautical experience, of which just over 120 hours were in command of the B58. The pilot had completed their most recent operational proficiency check on 9 January 2022 with a line check on the B58 carried out on 25 January 2022.
Recorded Data
The aircraft was not fitted with a flight data recorder or cockpit voice recorder, nor was it required to be.
The operator tracked each of their aircraft using a Spidertracks unit. The system consisted of a device located in each aircraft that recorded and transmitted its position at two-minute intervals and allowed the pilot to signal an emergency or alert through a dedicated button on the device.
The operator also utilised the AvPlan electronic flight bag application for pilots to undertake flight planning. The application records position information at 5‑second intervals. The pilot of NPT had a device with the application installed and active for the flight and the ATSB received data for the accident flight. This provided multiple flight parameters including ground speed and tracking details for the aircraft from the time of take-off until it collided with terrain.
In addition, the aircraft was fitted with a transponder that broadcast ADS-B[7] data to ground stations and nearby aircraft fitted with ADS-B IN. The ATSB was able to retrieve the data transmitted by this unit from ground stations operated by both Airservices Australia and other third-party receivers, including one at the East Kimberly Regional Airport.
The ATSB also obtained and reviewed relevant radio communications from the Brisbane Centre and common traffic advisory frequencies.
Meteorological Information
An aerodrome meteorological report (METAR[8] was issued by the automatic weather station at East Kimberley Regional Airport approximately 7 minutes before NPT collided with terrain. The report showed fine weather, with winds from the north at 2 kt, visibility greater than 10 km and nil cloud detected.
The ATSB also reviewed CCTV footage from the East Kimberley Regional Airport. Figure 5 shows the location of a camera covering the regular public transport apron, with the threshold of runway 12 in the background. The camera image showed, consistent with the METAR, a smoke plume rising near-vertically from the accident site approximately 3 minutes after the accident indicating little to no wind immediately after the accident.
Figure 5: Location of CCTV camera
Source: Google Earth annotated by the ATSB
Related occurrence
The ATSB identified another in-flight fire in a BE58 that contained similarities to this occurrence.
On 26 February 2014 at about 1645 local time, a Beech 58 aircraft, registered VH‑SBS, departed Darwin for Gove, Northern Territory, on a private ferry flight with a supervising pilot and pilot in‑command-under-supervision (ICUS) on board.
At about 1815, the pilot detected fumes and smoke emanating from within the cockpit. The pilot flying ICUS saw smoke and flames by their left leg adjacent to the circuit breaker panel and immediately switched off the electrical master switch. The supervising pilot seated in the right seat took control of the aircraft and commenced an immediate descent. The pilot ICUS retrieved the BCF extinguisher from underneath their seat and extinguished the fire
An engineering inspection found electrical wiring had penetrated through the heater supply fuel line causing it to arc out and burn a hole in the fuel line. With an ignition source and fuel, the fire in the cabin was started. Engineers disconnected and capped the heater fuel line and reconnected the vacuum line.
The engineer also reported that the wires had been bundled together and were rubbing on the fuel line. Inspection of the wires prior to the flight would have required the internal panel to be removed and was not a routine inspection item.
Safety advisory notice
Both the heater fuel line and the aircraft wiring of NPT were burnt away by the post impact fire, and an examination was not possible. However, the location, initiation and severity of the fire is similar to the incident detailed in AO‑2014‑040. As such, while the specific circumstances of the fire initiation and development remain under investigation, in the interest of transport safety, the ATSB has issued a safety advisory notice encouraging operators of B58 aircraft to:
note the circumstances of this accident and previous ATSB investigation AO‑2014‑040
conduct a detailed examination of the wiring and fuel line on the left side of the aircraft forward of, and behind, the pilot’s circuit breaker panel.
review the Electrical Wiring Chafing Protection section in Model Communiqué 116
review anti-chafing wiring provisions within the relevant aircraft maintenance manual to ensure serviceability of anti-chafing materials.
Further investigation
The investigation is continuing and will include analysis of recorded flight data and a review of:
the aircraft’s fuel and electrical systems
domestic and international related occurrences.
aircraft records
survivability aspects.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Acknowledgements
The ATSB wishes to acknowledge the assistance provided by the Western Australia Police Force, Helispirit and East Kimberley Regional Airport personnel during the onsite phase of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 3 April 2022, a Bell Helicopter 206L-4, registered VH-PRW, departed with a pilot and passenger on board, for a visual flight rules (VFR) flight from a private property at Majura, Australian Capital Territory to Mangalore, Victoria, with a planned refuelling stop in Tumut, New South Wales (NSW). The helicopter was one of 7 helicopters taking part in a flying tour that morning and the weather forecast indicated low cloud, rain and associated reduced visibility on the planned route.
Two of the 7 helicopters diverted to Wagga Wagga, NSW due to weather while 4 others landed near Wee Jasper, NSW. The pilot of VH-PRW elected to continue until they encountered poor weather conditions and landed the helicopter in the Brindabella region shortly before noon. At 1453 local time, the helicopter departed once again at low level, in overcast conditions with low cloud and light rain. At about 1525, the helicopter commenced a rapid climb and shortly after, entered a steep left descending turn which continued until the helicopter impacted terrain at an elevation of 4,501 ft. A search was initiated the next day with the accident site located later that evening. The helicopter was destroyed, and both occupants were fatally injured.
What the ATSB found
The ATSB found that, having encountered the forecast low cloud and reduced visibility conditions, the pilot landed the helicopter at an interim landing site. Later that day, the helicopter then departed into cloud and visibility conditions unsuitable for visual flight. It is highly likely these cloud and visibility conditions resulted in the pilot experiencing a loss of visual reference and probably becoming spatially disoriented. This led to a loss of control and an unsurvivable collision with terrain.
In relation to visual flight rules pilots flying into areas of reduced visibility, some key messages to manage risk are:
Know your limits. VFR pilots should use a ‘personal minimums’ checklist to help control and manage flight risks through identifying risk factors that include marginal weather conditions. Only fly in environments that do not exceed your capabilities. For visual flight at night, ensure you are both current and proficient with disciplined instrument flight.
Plan ahead. Avoid deteriorating weather by conducting thorough pre-flight planning. Ensure you have alternate plans in case of an unexpected deterioration in the weather and making timely decisions to turn back or divert.
Don’t press on! Pressing on into instrument meteorological conditions with no instrument rating carries a significant risk of severe spatial disorientation due to powerful and misleading orientation sensations with no visual cues. Disorientation can affect any pilot, no matter what their level of experience.
Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On the morning of 3 April 2022, a Bell Helicopter 206L-4, registered VH-PRW, was to conduct a visual flight rules[1] (VFR) flight from a private property at Majura, Australian Capital Territory to Mangalore, Victoria with a planned refuelling stop in Tumut, New South Wales (NSW). The helicopter was one of 7 helicopters taking part in a flying tour, following a common itinerary but operating independently.
The weather forecast indicated that the planned route could be affected by low cloud, rain and associated reduced visibility. At about 0900 Eastern Standard Time,[2] two of the helicopters departed Majura. These helicopters encountered low cloud and elected to divert over lower terrain north of the Brindabella Ranges to Wagga Wagga, NSW.
At 1021, VH-PRW, with the pilot and one passenger on board, departed the property at Majura along with the remaining 4 helicopters. Recorded tracking data showed that VH-PRW initially tracked south‑east before turning west toward the Brindabella Ranges (Figure 1). The flight then proceeded south over Corin Dam before heading north to Wee Jasper. As the 5 helicopters approached Wee Jasper, they also encountered deteriorating cloud and visibility conditions. Four of the pilots elected to land on a property near Wee Jasper. The pilot of VH-PRW did not land but continued south to ‘attempt to find a way through to Tumut’.
Figure 1: Flight from Majura to Long Plain
Source: Google Earth and OzRunways, annotated by ATSB
At 1129, the pilot of VH-PRW encountered poor weather conditions and landed the helicopter alongside Long Plain Road in the Brindabella region, outside of mobile phone coverage.
Shortly after the helicopter landed, a passing motorist stopped and approached the helicopter. The pilot advised the motorist that they had landed to wait for better weather conditions before continuing the flight. The motorist arranged to check on the pilot and passenger during the motorist’s return journey later in the day if the helicopter had not already departed by that time.
At about 1230, when VH-PRW did not return to Wee Jasper and the pilot had not contacted other members of the tour, authorities were notified and a search for the helicopter was commenced.
At about 1415, the motorist returned along Long Plain Road and found that the helicopter had not departed. The motorist transported the pilot to a location that enabled phone contact and the pilot contacted the office of the tour organiser to advise of the safe landing. The pilot also stated that they intended to continue the fight following powerlines at about 50 ft above ground level (AGL). The tour organiser advised against this plan and then notified the other members of the tour and authorities of the landing. The motorist and pilot then returned to the helicopter.
Recorded flight tracking data showed that at 1453, the helicopter departed Long Plain Road, with the pilot and passenger on board. Two minutes later, one of the other pilots in the tour noted the helicopter tracking south on a flight tracking application.
Police officers dispatched to locate the helicopter arrived at the landing site just after it became airborne. The motorist and police officers observed the helicopter depart to the south at low level, in overcast conditions with low cloud and light rain. The police officers stated that the helicopter passed ‘at a similar height or slightly above the powerlines’ before being obscured by low cloud.
The flight then progressed at heights below 500 ft AGL following geographical features along lower lying terrain (Figure 2). At 1504, the flight turned north-west and took up a track that corresponded with a direct track to Tumut. Two minutes later, the helicopter encountered higher terrain and turned around to head southward, again following lower lying terrain. At 1517, in the vicinity of Anglers Reach, the flight turned north. Two minutes later, the helicopter turned to the north-west, again along a flightpath that corresponded with a direct track to Tumut and commenced a climb to about 7,000 ft above mean sea level (AMSL).
Figure 2: Accident flight
Source: Google Earth and OzRunways, annotated by ATSB
The helicopter continued along that track at groundspeeds of 105‑115 kt until 1525 when it descended to 6,800 ft. The helicopter then almost immediately commenced a rapid climb. As the helicopter climbed, the recorded groundspeed reduced. After reaching 7,400 ft at a groundspeed of 60 kt, the helicopter entered a steep left descending turn.
The descending turn continued until the helicopter impacted terrain at an elevation of 4,501 ft at about 1526. The helicopter was destroyed, and both occupants were fatally injured.
On 4 April, in response to the helicopter not re-joining the tour as expected, a second search was initiated. At about 2355, a ground search assisted by helicopter tracking data located the accident site.
Context
Pilot information
The pilot held a valid class 2 medical certificate and a private pilot licence (helicopter).
At the time of the accident, the pilot had about 837 hours of aeronautical experience and did not hold an instrument rating. The pilot’s total flying experience on the Bell 206 was about 532 hours of which about 355 were in the L-4 variant and the remainder in the B-3 variant.
The ATSB found no indicators that increased the risk of the pilot experiencing a level of fatigue known to affect performance.
The post-mortem examination and a review of the pilot’s medical history identified no evidence of a medical event or pre-existing condition that likely contributed to the accident.
Aircraft information
The Bell Helicopter 206L-4 is a 7‑seat, single‑turboshaft engine helicopter equipped with 2-bladed main and tail rotors. VH-PRW was built in 2008 and first registered in Australia in 2016. At the time of the accident, the helicopter had completed about 830 hours in service and was certified for day VFR flight only. The helicopter was fitted with an emergency locator transmitter.
The helicopter was also fitted with the HeliSAS stability augmentation system. This used attitude data and electro-mechanical servo actuators connected to the flight controls rods to apply small corrections to the cyclic as required to maintain a reference attitude. The reference attitude could be set as required by the pilot. The system also incorporated a two-axis (pitch and roll) autopilot.
Tour coordination
The flight from Majura to Mangalore was part of an informal multi-day flying tour involving 7 helicopters. This tour was mostly coordinated by a helicopter operator who provided the itinerary and organised logistic details such as accommodation and fuel availability.
The tour organiser also operated a helicopter flying training and transport operation, but this tour was conducted outside of that operation. The tour organiser held no authority or responsibility for the operation of each involved helicopter, this responsibility was held by each pilot in command.
Terrain
The helicopter departed an interim landing site along Long Plain Road in the Brindabella Ranges. The flight then proceeded over rugged alpine areas of the Snowy Mountains with terrain elevations generally higher than 4,000 ft AMSL. Peaks of 5,854 ft AMSL and 5,726 ft AMSL were located near the final flight track (Figure 3).
Figure 3: Visual navigation chart extract showing terrain in the vicinity of the accident
Source: Airservices Australia and OzRunways, annotated by ATSB
Meteorology
Forecast
The graphical area forecast for the accident region provided a forecast icing level of 10,000 ft AMSL and the following cloud and visibility conditions for the time of the accident (all heights AMSL):
Generally greater than 10 km visibility with broken[3] cumulus/stratocumulus cloud between 2,500 ft and 10,000 ft.
Visibility reducing to 4,000 m in scattered rain with broken stratus cloud between 1,500 ft and 6,000 ft. Overlying this, broken altocumulus and altostratus cloud could be expected extending from 6,000 ft to above 10,000 ft.
Visibility reducing to 3,000 m in scattered rain showers with broken stratus cloud between 1,500 ft and 3,000 ft. Overlying this, broken cumulus and stratocumulus could be expected extending from 3,000 ft to above 10,000 ft.
Photograph
A photograph taken 2 minutes prior to the helicopter departing Long Plain Road showed the cloud conditions at that time (Figure 4). The elevation of the landing site was about 4,429 ft AMSL. The peak of the terrain visible behind the helicopter is 4,573 ft AMSL. This peak was obscured by broken cloud indicating that the cloud base was less than 144 ft AGL.
Figure 4: Cloud conditions 2 minutes prior to departure from interim landing site
Source: motorist via NSW Police Force
Recorded observations
At 1530 (4 minutes after the accident), Bureau of Meteorology weather stations at Cabramurra (14 km south-west of the accident site, elevation 4,864 ft) and Mount Ginini (43 km north‑east of the accident site, elevation 5,774 ft) recorded no rainfall and no separation between the dew point temperature and air temperature. This indicated the presence of very low-level cloud, likely down to ground level at both stations. Neither station was equipped to provide more detailed cloud information.
Visual flight rules
Visual meteorological conditions
The Civil Aviation Safety Regulation (CASR) 91.280 outlined that flight under the visual flight rules (VFR) can only be conducted in visual meteorological conditions (VMC). The criteria are provided in the CASR Part 91 Manual of Standards Table 2.07 (3) and the CASA Visual Flight Rules Guide:
The flight, and the location of the accident, were in Class G (non-controlled) airspace. The following VMC were stipulated for flight under the VFR in Class G airspace when below 10,000 ft and above 3,000 ft or 1,000 ft above ground level (whichever is higher):
a minimum vertical distance of 1,000 ft and horizontal distance of 1,500 m from cloud
a flight visibility of 5,000 m.
For helicopter operations in Class G airspace at or below 3,000 ft or 1,000 ft above ground level (whichever is higher), the following minimum conditions were stipulated:
clear of cloud and in sight of the ground or water
a flight visibility of 5,000 m or, if operated by day at a speed that allows the pilot to see obstructions or other traffic in sufficient time to avoid collision, 800m.
Minimum height
In addition to minimum visibility and distance from cloud requirements, a pilot is also required to maintain a minimum height above the ground. Unless during take-off, landing or other approved low-flying operation, CASR 91.265 and 91.267 detail that a pilot in command must not fly a helicopter over:
any city, town, or populous area at a height lower than 1,000 ft above the highest feature or obstacle within a horizontal radius of 300 m of the point on the ground or water immediately below the helicopter; or
any other area at a height lower than 500 ft above the highest feature or obstacle within a horizontal radius of 300 m of the point on the ground or water immediately below the helicopter.
The investigation identified no evidence to indicate that the pilot intended to undertake an approved low-flying operation.
Recorded data
On-board the helicopter was a mobile device with the OzRunways electronic flight bag application installed. The application had an option for live flight tracking enabled that transmitted the device’s position and altitude. This data was also obtained by the ATSB.
The data showed that at 1519:22 the helicopter turned to a track that corresponded with the direct track to Tumut and 15 seconds later commenced a climb from low level to about 6,600 ft. At 1522:02, a further climb commenced, reaching 7,000 ft at 1522:42. The helicopter continued to track generally toward Tumut at groundspeeds of 105‑115 kt, corresponding to a normal cruise speed for the helicopter. During this segment of the flight, track variations of up to 21° and altitude variations of up to 300 ft were recorded.
At 1525:22, the helicopter descended from 7,000 ft, reaching 6,800 ft about 20 seconds later. From 6,800 ft, a climb was commenced and a further 20 seconds later, the helicopter reached 7,400 ft (at climb rate of 1,800 ft per minute) with a groundspeed of 60 kt. The helicopter then entered a steep left descending turn. During the turn, the groundspeed increased to 137 kt and the descent rate exceeded 3,800 feet per minute (Figure 5).
Figure 5: Aircraft flight path leading up to the accident
Source: Google Earth and OzRunways, annotated by ATSB
Site and wreckage information
The accident site was located within the Kosciuszko National Park in an area of tussock grass, interspersed by bare protruding rock (Figure 6).
Figure 6: Accident site
Source: ATSB
The helicopter collided with terrain between two rock formations in a descending tight left turn and right side-slip in a northerly direction with a westerly heading. At initial impact, a main rotor blade struck the ground and the tail boom separated. The fuselage then turned left to about a southerly heading. Most of the wreckage was located within 8 m of the impact, but the main transmission, mounts and supporting airframe structure continued a further 70 m up an incline. On-site examination indicated that the engine was providing power at impact. There was no evidence of an in-flight break-up or a pre-existing defect with the drive train or flight controls.
The emergency locator transmitter (ELT)[4] antenna separated from the unit during the impact sequence. The ELT was examined at the ATSB’s technical facilities in Canberra and was found to have activated during the accident. However, the separation of the antenna prevented a signal from being broadcast. While this delayed search and rescue efforts, it did not alter the outcome as the accident was not survivable.
Risks of flying in areas of reduced visual cues
The safety risks of VFR pilots flying from VMC conditions into instrument meteorological conditions[5] are well documented. This has been the focus of numerous ATSB reports and publications, as VFR pilots flying into IMC represents a significant cause of aircraft accidents and fatalities. In 2013, the ATSB Avoidable Accidents series was re-published. Of these publications, the booklet titled Accidents involving pilots in Instrument Meteorological Conditions outlined that:
In the 10 years to July 2019, 101 VFR into IMC occurrences in Australian airspace were reported to the ATSB. Of those, 9 were accidents resulting in 21 fatalities. That is, about 1 in 10 VFR into IMC events result in a fatal outcome.
Spatial disorientation
Spatial disorientation is a type of loss of situation awareness, and is different to geographical disorientation, or incorrectly perceiving the aircraft’s distance or bearing from a fixed location. Spatial disorientation occurs when pilots do not correctly sense their aircraft’s attitude, airspeed, or altitude in relation to the earth’s surface. In terms of an aircraft’s attitude, spatial disorientation is often described simply as the inability to determine ‘which way is up’, although the effects can often be more subtle than implied by that description.
Spatial disorientation occurs when the brain receives conflicting or ambiguous information from the sensory systems. It is likely to happen in conditions in which visual cues are poor or absent, such as in adverse weather or at night. Spatial disorientation presents a danger to pilots, as the resulting confusion can often lead to incorrect control inputs and resultant loss of aircraft control. The flight control sensitivity and relative instability of helicopters compared to aeroplanes increases the risk of such a control loss.
Related occurrences
There have been many accidents relating to VFR pilots flying into reduced visibility conditions. The ATSB publication listed above identifies a number of similar occurrences. Of note is investigation AO-2015-131.
At about 5.30 pm on 7 November 2015, the owner-pilot of an Airbus Helicopters (Eurocopter) EC135 departed Breeza, NSW, on a VFR private flight with two passengers on board to Terrey Hills, NSW.
Witnesses observed the helicopter land in a cleared area in a valley. After 40 minutes on the ground, the pilot, who did not hold an instrument rating and was limited to visual flight operations, departed to the east towards rising terrain in marginal weather conditions. About seven minutes later, and approximately 9 km east of the interim landing site, the helicopter collided with terrain resulting in fatal injuries to all occupants.
The ATSB found that the pilot likely encountered reduced visibility conditions leading to loss of visual reference leading to the collision with terrain.
Safety analysis
While en-route from Majura, Australian Capital Territory, to Tumut, New South Wales, a group of 5 helicopters including a Bell Helicopter 206L-4, registered VH-PRW, encountered deteriorating cloud and visibility conditions. The pilots of 4 of the helicopters landed at Wee Jasper, but the pilot of VH-PRW continued south into the Brindabella Ranges. After encountering further low cloud and poor visibility, the pilot of VH-PRW landed the helicopter alongside Long Plain Road in the ranges.
At 1453, the pilot decided to depart the interim landing site and continue the flight. The flight progressed for 32 minutes until the helicopter commenced a rapid climb and then a descending left turn which continued until the helicopter collided with terrain.
Site and wreckage examination did not identify any defects or anomalies that might have contributed to the accident. Additionally, there was no evidence to support the pilot being incapacitated. Therefore, this analysis will focus on the examination of the factors that led to a visual flight rules (VFR) pilot operating in an area of reduced visibility and losing control of the helicopter.
Departure into unsuitable conditions
Low cloud and poor visibility conditions were forecast across the Brindabella Ranges on the day of the accident. The pilot, having encountered these conditions, landed the helicopter alongside Long Plain Road at 1129. The pilot and passenger then waited for conditions to improve sufficiently to depart the interim landing site.
Despite no such improvement eventuating, after about 3 hours and 24 minutes, the pilot elected to depart and continue to Tumut at about 50 ft above ground level. Photographs, along with police and witness reports, showed that at the time of the departure the cloud and visibility conditions were unsuitable for visual flight. The broken cloud base of less than 144 ft did not allow the pilot to maintain the helicopter both, clear of cloud as required by visual meteorological conditions (VMC) and at the minimum height above terrain of 500 ft.
Departing into unsuitable cloud and visibility conditions, particularly in the vicinity of mountainous terrain at very low level carried significant risk of both losing visual reference and of collision with terrain.
Loss of control
After departing the interim landing site, the flight proceeded at very low level for 26 minutes until the pilot turned the helicopter to a more direct track toward Tumut and climbed to about 7,000 ft above mean sea level (AMSL).
Observations recorded at meteorological stations in the vicinity of the flight indicated that it was highly likely that there was low cloud in the area of the accident. In addition, significant cloud was forecast and observed from ground level to above 10,000 ft AMSL along the flown track. In these conditions it was highly likely that VMC could not be maintained and that reduced visual cues were encountered by the pilot.
Over the next 6 minutes, minor tracking and altitude variations were recorded. It is possible these variations resulted from attempts to manoeuvre around, or in, cloud or rain showers with associated reduced visibility. Additionally, this manoeuvring indicates that the autopilot was not being used during this part of the flight. It could not be determined if the stability augmentation system was being used.
The flight at about 7,000 ft continued until 1525:42 when a rapid climb of about 1,800 ft per minute was commenced. This was immediately followed by a steep descending left turn. This manoeuvring was inconsistent with normal helicopter operation and was indicative of a loss of control.
The pilot did not hold an instrument rating and the helicopter was certified for day visual flight only. This greatly increased the risk of the pilot being affected by special disorientation and it is unlikely the pilot could have maintained control without visual reference for an extended period. Given the forecast and observed conditions, it is likely that during the 6 minutes the helicopter was operating at the higher level, it encountered poor weather. This likely led to the pilot experiencing spatial disorientation which resulted in a loss of control and the collision with terrain.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision with terrain involving Bell Helicopter 206L-4, VH-PRW, on 3 April 2022.
Contributing factors
Having landed the helicopter at an interim landing site due to encountering forecast low cloud and reduced visibility conditions, the pilot subsequently departed into cloud and visibility conditions unsuitable for visual flight.
It is highly likely that cloud and visibility conditions resulted in the pilot experiencing a loss of visual reference and probably becoming spatially disoriented. This led to a loss of control and an unsurvivable collision with terrain.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
NSW Police Force
the occupants’ next of kin
Civil Aviation Safety Authority
tour organiser.
Submissions were received from:
Civil Aviation Safety Authority
the passenger’s next of kin
tour organiser.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to allow the pilot to see where the aircraft is going.
[2] Eastern Standard Time (EST): Coordinated Universal Time (UTC) + 10 hours.
[3] Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘scattered’ indicates that cloud is covering between a quarter and a half of the sky, ‘broken’ indicates that more than half to almost all the sky is covered.
[4] Emergency locator transmitter (ELT): a radio beacon that transmits an emergency signal that may include the position of a crashed aircraft, activated either manually or in the crash.
[5] Instrument meteorological conditions (IMC): weather conditions that require pilots to fly primarily by reference to instruments, and therefore under Instrument Flight Rules (IFR), rather than by outside visual reference. Typically, this means flying in cloud or limited visibility.
Preliminary report
Report release date: 05/08/2022
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On the morning of 3 April 2022, a Bell Helicopter 206L-4, registered VH-PRW, departed from a private property at Majura, Australian Capital Territory for a visual flight rules[1] (VFR) flight to Mangalore, Victoria. The flight departed with the pilot and one passenger on board and included a planned refuelling stop in Tumut, New South Wales (NSW). The aircraft was one of 7 helicopters taking part in a flying tour, following a common itinerary but operating independently.
The weather forecast indicated that the planned route could be affected by low cloud, rain and associated reduced visibility. At about 0900 Eastern Standard Time,[2] the tour organiser departed Majura in a helicopter to observe the weather along the planned route. Based on their assessment of the en route weather, the organiser recommended that the flights should track north of the planned route and refuel at Wagga Wagga, NSW.
Recorded flight tracking data showed that at 1021, VH-PRW departed the property at Majura. The helicopter initially tracked south‑east before turning west toward the Brindabella Ranges (Figure 1). The flight then proceeded south over Corin Dam before heading north to Wee Jasper. After passing Wee Jasper, the flight again turned south toward the ranges.
Figure 1: Flight from Majura to Long Plain
Source: Google Earth and OzRunways, annotated by ATSB
During their flights, the occupants of the other helicopters in the tour encountered deteriorating cloud and visibility conditions and landed on a property near Wee Jasper. When VH-PRW did not arrive, authorities were notified and commenced a search for the helicopter.
At 1129, the pilot of VH-PRW landed the helicopter alongside Long Plain Road in the Brindabella region. Shortly after the helicopter landed, a passing motorist on Long Plain Road stopped and approached the aircraft. The motorist transported the pilot to a location that enabled phone contact with other members of the tour. The pilot advised other members of the tour of the safe landing and that the intended destination had been Tumut, not Wagga Wagga as recommended by the tour organiser. The motorist and pilot then returned to the aircraft.
Recorded flight tracking data showed that at 1453, the helicopter departed Long Plain Road with the pilot and passenger on board. Police officers dispatched to locate the helicopter arrived at the landing site just after it became airborne. The motorist and police officers observed the aircraft depart to the south at low level, in overcast conditions with low cloud and light rain.
The flight progressed at heights below 500 ft above ground level (AGL) following geographical features along lower lying terrain. At 1504, the flight turned north‑west and took up a track that corresponded with a direct track to Tumut. Two minutes later, the helicopter encountered higher terrain and turned around to head southward, again following lower lying terrain. At 1517, in the vicinity of Anglers Reach, the flight turned north (Figure 3). Two minutes later, the helicopter turned to the north‑west, again along a flightpath that corresponded with a direct track to Tumut and commenced a climb to 7,000 ft above mean sea level (AMSL) (about 2,500 ft AGL).
Figure 2: Accident flight
Source: Google Earth and OzRunways, annotated by ATSB
The helicopter continued along that track at about 7,000 ft AMSL for 6 minutes until 1525. The helicopter then descended to 6,800 ft, before almost immediately climbing. After reaching 7,400 ft, the helicopter commenced a steep left descending turn. During the turn, the ground speed increased to 134 kt and the descent rate exceeded 3,800 feet per minute.
At 1526, the aircraft impacted terrain at an elevation of 4,501 ft. The helicopter was destroyed, and both occupants were fatally injured.
On the morning of April 4, in response to the aircraft not arriving at Mangalore as expected, a second search was initiated. Poor weather prevented an airborne search. At about 2355, a ground search assisted by aircraft tracking data located the accident site.
Context
Pilot information
The pilot was the aircraft owner and held a valid class 2 medical certificate and a private pilot licence (helicopter).
At the time of the accident, the pilot had about 837 hours of aeronautical experience and did not hold an instrument rating. The pilot’s total flying experience on the Bell 206 was about 532 hours of which about 355 were in the L-4 variant and the remainder in the B-3 variant.
Aircraft information
The Bell Helicopter 206L-4 is a 7‑seat, single‑turboshaft engine helicopter equipped with 2-bladed main and tail rotors. VH-PRW was built in 2008 and first registered in Australia in 2016. At the time of the accident, the helicopter had completed about 830 hours in service and was certified for day VFR flight only.
Meteorological information
The graphical area forecast for the area at the time of the accident indicated broken[3] cumulus/stratocumulus cloud with a base of 2,500 ft AMSL and a top of 10,000 ft AMSL.
At 1530 (4 minutes after the accident), Bureau of Meteorology weather stations at Cabramurra (14 km south‑west of the accident site, elevation 4,864 ft) and Mount Ginini (43 km north‑east of the accident site, elevation 5,774 ft) recorded no rainfall and zero separation between the dew point temperature and air temperature. This indicated cloud was present at both stations, however neither station was equipped to provide more detailed cloud information.
Site and wreckage information
The accident site was located within the Kosciuszko National Park in an area of tussock grass, interspersed by bare protruding rock (Figure 3).
Figure 3: Accident site
Source: ATSB
The helicopter collided with terrain between two rock formations in a descending tight left turn and right side-slip in a northerly direction with a westerly heading. At initial impact, a main rotor blade struck the ground and the tail boom separated. The fuselage then turned left to about a southerly heading. Most of the wreckage was located within 8 m of the impact, but the main transmission, mounts and supporting airframe structure continued a further 70 m up an incline. On-site examination indicated that the engine was providing power at impact. There was no evidence of an in-flight break-up or a pre-existing defect with the drive train or flight controls.
Further investigation
The ATSB investigation to date has examined the accident site and wreckage, interviewed witnesses, collected meteorological data, pilot and flight records and obtained aircraft tracking data.
The investigation is continuing and will include further review and examination of:
pilot records and medical information
aircraft maintenance and flight records
aircraft wreckage and recovered components
emergency locator transmitter functionality
witness information
meteorological data
recorded aircraft tracking data.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
Section 21 (2) of the Transport Safety Investigation Act 2003 (TSI Act) empowers the ATSB to discontinue an investigation into a transport safety matter at any time. Section 21 (3) of the TSI Act requires the ATSB to publish a statement setting out the reasons for discontinuing an investigation. The statement is published as a report in accordance with section 25 of the TSI Act, capturing information from the investigation up to the time of discontinuance.
Overview of the investigation
On 28 March 2022, the ATSB commenced an investigation into a hard landing involving a E-240 Kavanagh balloon, registration VH-ZON, which occurred at Moorabbin Airport, Victoria, on 27 March 2022.
The balloon was being operated on a scenic passenger flight between Reservoir and Moorabbin Airport with a pilot and 10 passengers on board. The pilot provided the operator’s standard safety briefing to the passengers before take-off, while the passengers were in the basket, to explain and demonstrate the position to adopt during normal landings and emergencies. The position was facing opposite to the landing direction, standing with slightly bent knees, holding on to the rope handholds in front, and back rested against padding on the basket. Passengers were to remain in that position until the basket stopped.
There were several other balloons operating the same scenic flight route, and the pilots had collectively decided the departure point and that the weather was suitable for their respective flights (all along the same route). The pilots reviewed several sources of weather information, including the Bureau of Meteorology aerodrome forecasts (TAF) for Melbourne, Essendon and Moorabbin. The Moorabbin TAF forecast the wind to be 11 kt from the north-east at the time the balloons were due to land.
The pilots had also obtained information about the actual wind conditions prior to departure by releasing 2 piballs[1] in different locations to assess the speed and direction of the wind at different levels. Following this assessment, the balloons departed at about 0700 local time.
The pilot had about 30 years experience as a balloon pilot and had been operating balloons in the area for about 18 years, with extensive knowledge of the planned route.
On approach to Moorabbin Airport, VH-ZON was travelling in a south-easterly direction and was about 500 m to the west of the other balloons. The pilot obtained automatic terminal information by radio for Moorabbin, and it advised of a 4-kt north-easterly surface wind.
The pilot reported that they had commenced the descent into Moorabbin Airport after the other balloons and found the wind to be faster at the lower levels than expected. Data collected via another balloon pilot’s navigation equipment post-accident showed the wind was about 38 kt at 1,400 ft and 35 kt at 1,000 feet, which was significantly faster than the pilots had anticipated. This meant that the pilot had to conduct a faster than usual descent to ensure they could land the balloon in a suitable area.
When the balloon reached 300–400 ft, it travelled through a temperature inversion (where temperature increases with altitude, which is a reversal of typical atmospheric conditions) and the balloon rotated 120°. Although the passengers had been instructed to adopt the landing position, the pilot did not have time to rotate the balloon to the correct orientation (with the passengers facing opposite to the landing direction) before reaching the ground. On landing, the balloon impacted the front right corner of the basket and bounced. The basket was then dragged for a short distance, coming to rest in a culvert at the end of a runway within the airport boundary.
As a result of the hard landing and the orientation of the basket, 1 passenger was seriously injured and 2 passengers received minor injuries.
As part of its investigation, the ATSB interviewed the pilot and passengers and reviewed:
weather information including observations and forecasts used by the pilot
air traffic control recordings
recorded navigation information used in-flight by one of the other balloon pilots (data could not be retrieved from the equipment used on the accident balloon)
the operator’s procedures for passenger briefings
photographs taken in-flight by the balloon operator and others that were provided by passengers and a witness on the ground.
The ATSB notes that, due to unexpected wind speed on descent (which was much higher than the surface wind information that the pilot had previously obtained), and the limited landing site options, the pilot decided to land as soon as possible. This resulted in a faster and harder landing than normal. The balloon’s abnormal orientation after passing through the temperature inversion meant that although the passengers were in the correct position for landing, there was a greater risk of injury.
Reasons for the discontinuation
Based on a review of the available evidence, the ATSB considered it was unlikely that further investigation would identify any systemic safety issues or important safety lessons from this specific occurrence. Consequently, the ATSB has discontinued this investigation.
However, the ATSB is concerned about the number of accidents that have been occurring in commercial balloon operations and has listed the reduction of passenger injuries in commercial ballooning operations as one of its Safety Watch items. The evidence collected during the investigation involving VH-ZON will be used in a safety study further examining these types of accidents.
[1] Piball: an abbreviation of ‘pilot balloon’, which is a small, helium-filled free balloon with a light attached. It is released and visually tracked to determine the wind at different altitudes.
On 3 March 2022, the pilot of a Cessna U206G, registered VH-JVR and operated by MAGSPEC Aviation Pty Ltd, was conducting a low-level geophysical survey, about 120 km west of Norseman, Western Australia. Recorded data showed the first survey line commenced at 1252 local time, and the aircraft’s last recorded position occurred at 1343, in the survey area.
At about 1430, the ground operator observed that the satellite tracking system was no longer reporting the aircraft’s position, and they were subsequently unable to contact the pilot. When the aircraft failed to return to Kalgoorlie by its estimated arrival time of 1630, a search was initiated. At about 1852, the wreckage was located 3.2 km west of the aircraft’s last recorded position. The injured pilot had extricated themselves from the wreckage but shortly after succumbed to their injuries. The aircraft was destroyed.
What the ATSB found
The ATSB found it was likely that, during a manoeuvre to intercept the next survey line, for undetermined reasons, control of the aircraft was lost at a height from which recovery was not possible. While an aerodynamic stall situation was a plausible explanation for the loss of control, this remained only a possibility due to the lack of recorded data beyond the last known position of the aircraft and no witness observations.
Although the aircraft’s satellite tracking system had stopped at 1343, an emergency response was not initiated until 1700. This was in accordance with the operator’s emergency response plan, in which a search and rescue response was to commence 30 minutes after the estimated time for arrival. However, an earlier response was very unlikely to have altered the outcome due to the extent of the pilot’s injuries. Minimising the time for a search and rescue is essential to increasing the chances of a successful outcome in the event of an accident.
In accordance with the operator’s training, its pilots routinely used high angle of bank (45–60°) turns at low level to manoeuvre between survey lines. Steep turns at low level increases the risk of an aerodynamic stall from which a recovery may not be possible. ATSB analysis of the available satellite tracking data identified that, although the pilot was conducting steep turns, they had flown the previous 24 turns without incident.
The pilot was not wearing any protective clothing or a helmet nor were they required to do so by the operator. Wearing of such items has been recommended by industry bodies, as they may offer some protection in the event of an accident, particularly from fire but also as environmental protection following an accident.
The ATSB identified that the operator’s risk management processes did not include a pre‑operational risk assessment that considered the generic risks and hazards common across their low‑level survey operations. Further, a risk register was not maintained, which limited the operator’s ability to track, monitor, and mitigate all known hazards, and assess the effectiveness of the existing risk controls.
Also, the operator trained its pilots to routinely fly survey patterns utilising steep turns at low level. However, the procedures or limitations specific to these manoeuvres were not included in the operations manual. It was also noted that, the operator’s aircraft were fitted with a satellite tracking system, but there was no requirement nor supporting procedures to confirm the set‑up and functionality of the system prior to flight.
Although not contributory, the ATSB identified that the regulatory oversight of the operator had not specifically examined the primary activity of low‑level geophysical survey flights or the processes and procedures designed to mitigate any associated risks.
What has been done as a result
MAGSPEC Aviation has consolidated its manuals, with its health, safety and environmental management system manual incorporated into its operations manual. In addition, it has implemented a range of measures regarding its low‑level survey operations including:
an updated job safety analysis, which provides for the consideration of likelihood, consequence and details of any risk mitigations
procedures for the use of satellite tracking including a requirement for a pre-flight check
conduct of procedure turns including how the turns should be flown, with minimum speeds indicated and what to do if those speeds could not be achieved
the requirement for fixed emergency locater transmitters on all aircraft, and limitations for flight if the unit is unserviceable or not present
updating its low-level training syllabus to include specific parameters (which mimic its previous practical training), so that competency can be formally assessed against those parameters.
MAGSPEC Aviation has also advised it no longer operates at survey heights below 30 m above ground level and it provides its pilots with an individually registered portable locator beacon, which they are required to wear on their person. It is also progressing operational amendments to enable Flight Safety Foundation’s Basic Aviation Risk Standard accreditation. Just prior to final publication of this report, the operator advised that it had been awarded the Basic Aviation Risk Standard accreditation.
Safety message
Geophysical survey operations are generally conducted at low level, necessitated by the requirement for high quality, accurate data acquisition. This creates a high‑risk operating environment that requires effective risk management.
Risk management should include a pre‑operational risk assessment to consider hazards and risks common to an operation. This can then be used to inform the management of risk for specific taskings and assist in developing appropriate mitigations. Tools such as a risk register can assist an organisation to effectively monitor its risk profile and continually improve its risk mitigation strategies.
Policy and procedures form part of effective risk mitigation strategies and will establish safety and the operating standards to be met and maintained. Documented policies and procedures can ensure the correct set‑up and functionality of operating equipment and systems. It can also minimise opportunities for deviation from an operator’s expectations and the erosion of safety margins.
This accident further highlighted that regulatory oversight activities should ensure that an operator’s primary activity is examined in sufficient detail. Not doing so potentially limits the opportunity to assess an operator’s ability to manage the risks associated with its proposed operations.
The occurrence
On 3 March 2022, a Cessna Aircraft Company U206G aircraft, registered VH-JVR, was being operated by MAGSPEC Aviation Pty Ltd for low-level, geophysical survey flights of an area about 120 km west of Norseman, Western Australia (Figure 1).
The aircraft was based at Kalgoorlie for this survey task along with 2 pilots and a ground operator. One pilot would operate the aircraft in the morning and the other in the afternoon. The ground operator was responsible for the technical and logistical aspects of the survey.
At about 1125 local time, at the completion of the morning survey flight, the aircraft was returned to Kalgoorlie. The second pilot commenced their pre‑flight preparations at about 1130 and discussed the morning survey flight with the returning pilot. That pilot advised of a minor concern about a fuel imbalance that developed during the approximate 4‑hour flight, however, they did not report any impact on aircraft handling or engine operation.
The ground operator prepared the survey equipment and assisted the pilot to fully fuel the tanks.
Figure 1: VH-JVR's operating area in proximity to Kalgoorlie and Norseman
Source: Operator’s satellite tracking data, overlaid on Google Earth, annotated by the ATSB
At about 1200, the aircraft departed for the survey area with the pilot as the sole occupant. Recorded GPS data showed that the first survey line was commenced at about 1252, picking up where the morning survey flight had been completed. The last position uploaded to the tracking system was at 1343, which showed the aircraft was on a westerly heading at a ground speed of 116 kt and a GPS height of 1,398 ft above mean sea level in the target survey area.
At about 1430, the ground operator checked the satellite tracking system for VH‑JVR and noted that the aircraft’s position was no longer being reported on the system.The satellite tracking system had the ability to automatically alert the operator 15 minutes after tracking data was no longer being uploaded to the system’s servers. The operator reported they did not receive an automatic alert.
The ground operator then attempted unsuccessfully to call and text the pilot’s mobile phone. Although the aircraft carried a satellite phone as part of its survival kit, it was not routinely switched on during operations. The ground operator then advised the operations manager, who directed them to continue the attempts at making contact and prepare the ground vehicle for a potential response. Further attempts at contact were unsuccessful and the operations manager directed that no further action could be taken other than to monitor the situation and wait until the aircraft’s estimated time of arrival at Kalgoorlie.
The aircraft did not return to Kalgoorlie by the estimated time of arrival of 1630. At 1700, in accordance with its emergency response plan, the operator contacted the Australian Maritime Safety Authority’s Joint Rescue Coordination Centre (JRCC). Another company aircraft and pilot that was at Norseman was dispatched by the operator to VH-JVR’s last known position, however, the pilot was not able to locate the aircraft.
The JRCC initiated a search and rescue operation at 1739. The aircraft wreckage was located at 1852, approximately 3.2 km west of its last recorded position (Figure 2). The search aircraft’s crew were unable to establish communications with the pilot of VH‑JVR. The JRCC also deployed a rescue helicopter to the site, and at 0042, they found the pilot, fatally injured a short distance from the wreckage.
Figure 2: VH-JVR's accident site location and last recorded position
Source: Operator’s satellite tracking data, overlaid on Google Earth, annotated by the ATSB
Context
Pilot information
Qualifications and experience
The pilot held a commercial pilot licence (aeroplane) issued in 2014 and a valid class 1 aviation medical certificate. They held a multi‑engine aeroplane instrument rating and a grade 3 instructor rating, although neither were current, nor were they required to be.
At the time of the accident, the pilot had about 1,822 hours total aeronautical experience, of which about 570 hours were with the operator, primarily in Cessna 210 aircraft. The pilot had accrued over 350 hours on Cessna 206 aircraft prior to joining the operator and had about 12 hours on VH‑JVR.
The pilot commenced and completed a low‑level (aeroplane) rating in June 2021, which comprised 6.7 hours of dual training in a Cessna 152 aircraft, including a flight test. In July 2021, the pilot then commenced low‑level survey training with the operator in a Cessna 210 aircraft. The pilot’s logbook detailed 5 initial training survey flights totalling 18.6 hours. These were followed by about 21 hours of solo low‑level survey, culminating in a check flight of 5.6 hours.
The chief pilot (CP) conducted the pilot’s low‑level survey training and their geophysical survey operations check flight. The CP reported that the pilot ‘was one of those pilots who picked it up very quickly’ and was ‘very switched on’. In total, the pilot had conducted about 500 hours of low‑level survey operations.
Although the pilot had previously flown high‑level surveys, MAGSPEC Aviation was the first operator that the pilot had flown low‑level surveys for. The operator also reported that the pilot had been recently offered and had accepted the role of deputy chief pilot/deputy head of operations.
Recent history
The pilot had been on leave since 23 February 2022. The pilot’s partner reported that, on 1 March 2022, the pilot woke at about 0700, went to bed at about 1930–2000 and did not fly that day. On 2 March 2022, the day prior to the accident, the pilot woke at 0400 and arrived at Perth Airport at 0500 to take a scheduled passenger flight to Geraldton, where VH‑JVR had been undergoing scheduled maintenance. The pilot then ferried the aircraft about 700 km to Kalgoorlie, arriving around midday. Later that day, the pilot accompanied the second company pilot assigned to the survey area on a 30–40 minute local flight to familiarise the second pilot with VH‑JVR, as they had not previously flown that aircraft.
The pilot’s partner received a text message from the pilot at 1922, advising that they were cooking dinner in their accommodation and had no plans to go out that night. There was no further evidence of the pilot’s activities prior to the accident flight, but the pilot usually woke around 0600–0630, exercised and studied in the mornings before conducting the afternoon survey flight.
The day of accident was the first day of that survey task. Neither the other pilot nor the ground operator expressed any concern for the pilot. Based on the available recent history, there was no evidence the pilot was likely experiencing a level of fatigue at the time of the accident.
Aircraft information
General
The Cessna Aircraft Company U206G Stationair was a high‑wing, fixed tricycle undercarriage aircraft powered by a single Continental IO‑520‑F piston engine, with a 3‑bladed constant speed propeller. VH‑JVR was manufactured in 1978 in the United States and was first registered in Australia in 1998. The aircraft was acquired by the operator in 2021.
Factory fitted standard equipment included:
a vane‑type aerodynamic stall[1] warning system in the leading edge of the left wing designed to activate the audible warning horn 5–10 kt above the stall speed in all configurations
2 vented fuel wing tanks, which were an integral part of the metal wing structure[2] and supplied fuel via gravity feed to 2 reservoir tanks, and a fuel selector valve with selections for LEFT, RIGHT and OFF
3-point safety harness restraints.
Modifications
In October 2021, VH‑JVR had been modified and equipped to conduct geophysical survey operations in accordance with engineering orders approved by a Civil Aviation Safety Authority (CASA) authorised aeronautical engineer and supplemental type certificates.[3] These modifications included:
A magnetometer boom installed at the rear of the aircraft and associated survey equipment, with its own power supply, mounted in the rear cabin.
A fuel selector valve, which enabled the selection of LEFT/BOTH/RIGHT with a pull‑out fuel shut off valve installed to cut off fuel flow.
A survey data acquisition and navigation system, which included flight path guidance via a digital display mounted on top of the instrument panel, allowing the pilot to monitor aircraft position in relation to the pre-programmed survey lines.[4]
A 4-point inertia safety restraint harness.
Maintenance
The aircraft was being maintained by an approved maintenance organisation in accordance with the CASA maintenance schedule 5 and regulatory requirements. The last periodic inspection was completed on 2 March 2022 at 7,982.4 hours total time‑in‑service. The current maintenance release was not recovered and likely destroyed in the post‑impact fire. A review of previous maintenance releases and maintenance records did not identify any major repairs or recurring airworthiness issues with the aircraft.
Emergency locator transmitter
Civil Aviation Safety Regulations (CASR) 1998 Part 91 General operating and flight rules Manual of Standards (MOS) required that VH‑JVR carry an emergency locator transmitter (ELT) or a survival ELT for its intended operation. At the time of the accident, VH‑JVR was not fitted with an ELT but carried a survival ELT (refer to section titled Emergency beacons).
Weight and balance
The CP provided a recreated weight and balance sheet of the accident flight to the ATSB. The morning pilot witnessed the aircraft depart with full fuel in the survey configuration. The weight and balance sheet identified that VH‑JVR weighed about 1,488 kg on departure, about 150 kg below the maximum take‑off weight of 1,636 kg. The centre of gravity on take‑off was near the centre of the allowable range. Therefore, it was very likely that VH‑JVR was within the weight and balance limits at the time of take‑off.
Meteorological information
The pilot who flew the morning survey flight reported that the weather at that time was fine with good visibility, except for some light turbulence.
The Bureau of Meteorology forecast for the area, valid from 1300, was for visibility to be greater than 10 km and no significant weather for the time of the accident. Winds were forecast to be southerly at about 15 kt. Satellite imagery indicated no cloud cover over the survey area. The nearest weather stations to the accident site were at Norseman (124 km east) and Hyden (158 km west‑south‑west). There was no significant weather reported at either location. Recorded winds at 1330 were south‑westerly at about 14 kt at Norseman and south‑easterly at 10 kt gusting to 17 kt at Hyden.
According to Geoscience Australia’s geodetic calculator, the sun azimuth was north‑west at about 56° elevation about the time of the accident. This was relatively high in the sky and sun glare affecting the pilot was considered not likely.
Recorded data
Spidertracks data
A Spidertracks Spider X tracking system was installed on the aircraft, which provided near real‑time tracking via satellite and/or cellular networks, recording position, altitude, track heading and groundspeed at 15‑second intervals, increasing during aircraft manoeuvring. The data was transmitted to Spidertracks servers once every minute. The Spidertracks system also had an automatic watch function whereby an alert would be sent via text and email to a nominated person(s) in the event that the data transmissions from the device were not received for a period of 15 minutes.
Spidertracks data was able to be recovered for analysis due to its cloud‑based operation. The physical unit, and other possible data sources of recorded data identified in the wreckage, including personal electronic devices, the engine data monitoring device and the geophysical survey data equipment, were all damaged in the post‑impact fire, preventing data recovery.
The last known position transmitted by Spidertracks was about 3.2 km east, and approximately 1 minute away (at the last recorded speed) from the accident site (Figure 3). Position data was recorded by Spidertracks once every 15 seconds, increasing to about once every 3 seconds during a turn. However, as the data was only transmitted once every minute, it was likely that the accident occurred before Spidertracks was able to transmit the last data packet to the cloud storage.
The recovered data showed that the pilot had conducted procedure turns (refer to section titled Survey pattern) at the end of each of the completed 24 survey lines, over a period of about 50 minutes. Although all turns were observed to be conducted in a similar manner, one particular turn commenced at a greater distance away from the survey area. During interview, the CP suggested that the pilot may have done so in order to have a drink or attend to a flight‑related task. The ATSB noted no evidence to suggest any concern with this particular turn. The aircraft was on the 25th survey line when the data stopped, and the accident site was in the vicinity of the expected 25th procedure turn (Figure 3).
The recorded data showed the survey lines were being conducted in an east‑west orientation, with left turns conducted to the west and right turns to the east. The average survey line speed was 114 kt at an average height of about 78 ft above ground level (AGL).
Figure 3: Recorded flight path (excluding transit from Kalgoorlie)
Source: Operator’s satellite tracking data, overlaid on Google Earth, annotated by the ATSB
Procedure turn analysis
The available Spidertracks data was analysed to assess the aircraft handling during the accident flight. The recorded ground speed data and forecast wind and direction were used to estimate the true airspeed during the survey flight. Based on the available atmospheric conditions, true airspeed was assumed equal to indicated airspeed and is used throughout the following analysis.[5]
Using the available recordings, the average bank angle, rate of turn and G load for each turn for the accident flight were calculated. These calculations assumed steady coordinated turns, at constant altitude and airspeed, with a constant wind speed and direction.
The ATSB’s analysis of the Spidertracks data from the aircraft identified that during the procedure turns:
The angle of bank ranged from 43° to 60° and was typically between 50° to 60°.
The rate of turn ranged from 10° to 18° per second and was typically between 14° to 18° per second.
The G load[6] ranged from 1.3 G to 2 G and was typically about 1.7 G to 1.8 G.
The indicated airspeed ranged from 89 kt to 109 kt and was typically between 94 kt to 104 kt.
The altitude during turns were between 150 ft to 300 ft AGL, with the average being 200 ft.
Comparison flights
Spidertracks data from 2 previous flights for the accident pilot, which were in VH‑JVR, as well as the morning survey flight conducted in VH‑JVR by another pilot were made available to the ATSB. These were analysed for comparison to the accident flight.
Morning flight
The morning flight conducted by the other pilot consisted of 50 survey lines and 49 procedure turns. These survey lines were typically flown at 85 ft AGL and 120 kts. This set of survey lines were immediately adjacent to the accident flight survey, with the procedure turns occurring in a similar area. Analysis of these procedural turns identified:
The angle of bank ranged from 24° to 56° and was typically between 40° and 50°.
The rate of turn ranged from 4° to 16° per second and was typically between 10° and 13° per second.
The G load ranged from 1.1 G to 1.8 G and was typically between 1.3 G and 1.5 G.
The airspeed ranged from 92 kt to 109 kt and was typically between 95 kt and 104 kt.
The altitude during the turns varied between 210 ft and 550 ft, with the average being 320 ft AGL.
These turns, while generally comparable with the accident pilot’s turns, and considered steep turns,[7] were typically flown at lower angle of banks, rates of turn and G load, and at higher heights above ground level. The ATSB noted that the morning pilot had recently completed their survey training with the accident pilot on the Cessna 210. This was their first low‑level survey flight in the Cessna 206.
Previous flights (accident pilot)
Spidertracks data from 2 prior survey flights in VH‑JVR for the accident pilot were available. These flights were conducted in a different location, over undulating terrain with dense vegetation, with a higher average survey height of about 140 ft AGL at about 113 kt. Each flight consisted of just over 50 procedure turns and survey lines. A summary of the analysis of these procedural turns is contained in Table 1 below (refer flights 2 and 3), with comparison to the accident flight, and the morning pilot (flight 1).
Table 1: Comparative turn analysis results
Accident flight
Flight 1
Flight 2
Flight 3
Averaged turn radius (m)
197
277
280
248
Averaged angle of bank (°)
54
45
47
46
Averaged turn rate (°/s)
15
11
11
12
Averaged G load (G)
1.7
1.4
1.5
1.5
The ATSB’s analysis of the Spidertracks data from the pilot’s previous survey flights identified that those turns were flown at slightly lower angles of bank, rates of turn and G load when compared with the accident flight. While the pilot was operating at a different location, which may have influenced the way they conducted their turns, the reason for the differences was not able to be determined from the evidence available.
Wreckage and impact information
Wreckage distribution
The aircraft was located in moderately dense scrubland with small to medium trees. The terrain was relatively flat, with some low ridges in the surrounding area.
The distribution of the wreckage indicated that the aircraft initially struck trees in an upright orientation, with an approximate 20° left angle of bank, and a nose‑down attitude at about a 30° angle of impact. The initial tree strike resulted in the left wingtip and aileron separating from the aircraft. The aircraft then impacted the ground on its left side and continued through the bush in a southerly direction, coming to rest about 45 m from the initial point of impact, where it was consumed by a post‑impact fire.
The wreckage trail consisted of a number of felled trees and aircraft components, including the nose gear assembly, left main gear and fairing, left door, section of the left wing flap, windscreen and sections of the lower engine cowling and lower engine components. There was no indication of fire in the wreckage trail or detached aircraft components (Figure 4).
Figure 4: Wreckage trail looking north towards the impact area
Source: ATSB
The propeller had separated from the engine and was located towards the rear of the wreckage and the engine was upside down and detached from its mounts. Although the left wing was significantly affected by fire, the wing spar was still distinguishable. The right wing was relatively intact as was the magnetometer boom, albeit damaged by fire (Figure 5).
Figure 5: Main wreckage
Source: ATSB
Wreckage examination
Although post‑impact fire damage precluded examination of a significant proportion of the aircraft, inspection of the site and wreckage found:
no evidence of any pre‑existing structural, mechanical or flight control defects that would have prevented normal operation
the wing flaps were in the fully up (retracted) position
a small, yet intense fire zone indicative of a significant amount of fuel, with ignition occurring from the left‑wing integral fuel tank rupturing during the accident sequence
the fuel selector was in the ‘BOTH’ orientation
damage to the propeller indicated that the engine was producing power at the time of the impact.
Extensive fire damage to all instruments and avionics resulted in no useful switch position information. The windscreen, located part way along the debris trail, did not exhibit signs of birdstrike, nor were feather or bird remains identified in the area. In addition, the morning pilot reported that, while they had observed bird activity on survey flights, none had been sighted that day.
The reason for the fuel imbalance noted by the morning pilot could not be determined from the wreckage examination.
Medical and pathological information
Post-mortem examination
A post-mortem examination of the pilot was undertaken by a qualified pathologist on behalf of the Western Australia Coroner. The pathologist determined that the pilot’s cause of death was a result of a combination of traumatic injuries (both soft tissue injuries and multiple fractures) and the effects of fire from significant thermal injury and smoke inhalation. There were multiple fractures to the nasal bones but none to the skull or pelvis.
The pathologist assessed that the traumatic injuries sustained were potentially survivable with immediate medical assistance, but those injuries were compounded by the thermal injury and smoke inhalation. The ATSB’s aviation medical specialist also advised that the impact injuries were likely not fatal, however, they would have been severely incapacitating. The extensive thermal injury and, in particular, the smoke inhalation was likely to have rendered the pilot unconscious within minutes. They also stated that immediate intervention would have been required but the sustained thermal injuries were likely not survivable.
The post-mortem report indicated that the pilot did not have any significant natural disease. Further, toxicological analysis did not detect the presence of alcohol or common drugs and carbon monoxide[8] levels were not significantly raised (at less than 5% saturation).
The pilot was reported by their partner to be fit and healthy with no known illnesses.
Survival aspects
Impact protection
Due to extensive fire damage to the fuselage, there was limited evidence available about the survivable space/intrusions, or seat and seatbelt condition. Therefore, the ATSB was not able to determine survivability with regard to the cabin area. The left (pilot) door indicated an intrusion/compression and the left main landing gear leg was detached, consistent with high impact forces and the injuries sustained to the pilot.
Post-impact fire
Metal fuel tanks are prone to rupturing during an accident impact, allowing fuel to escape and increasing the risk of a post‑impact fire. To improve crashworthiness, the addition of fuel bladders and fuel cells that have been constructed of flexible materials have proven less prone to rupturing during an impact. They are able to withstand greater deformation and puncture less readily and are less likely to expand or tear to form a larger opening from which fuel can escape. Such systems may provide occupants with more time to egress the aircraft and/or reduce the risk of any fire‑related injury.
ATSB investigation report AO-2021-052, extensively discussed post‑impact fire safety and referenced studies by the United States National Transportation Safety Board and Transport Safety Board of Canada. Those studies concluded that post‑impact fire had been shown to contribute significantly to injuries and fatalities in accidents that were otherwise potentially survivable. A potentially survivable accident is one in which the impact forces are within the limits of occupant tolerance, the aircraft structure preserves the required survival space, and the occupant restraint is adequate.
As a result of investigation AO‑2021‑052, the ATSB identified that the aircraft (an Air Tractor AT‑400) was not required to be fitted with a crash‑resistant fuel system under United States Federal Aviation Regulations. A safety issue was raised and the ATSB recommended that the United States Federal Aviation Administration take action to address certification requirements for crash‑resistant fuel systems for fixed‑wing aircraft, in an effort to reduce the risk of post‑impact fire. At the time of writing this report, the ATSB recommendation remained open and the Federal Aviation Administration had advised that the results of a study into post‑crash fire accidents was being reviewed to determine their next action (AO‑2021‑052‑SI‑01).
Protective clothing and helmets
For the accident flight, the pilot was reported to be wearing a t‑shirt, shorts and trainer type shoes and was not using a helmet. The operator did not require its pilots to wear protective clothing or helmets, nor were they required to do so by regulations. The CP explained that this decision took into account temperature, fatigue and pilot comfort balanced against mitigating the potential risks. In addition to comfort and fatigue factors, the bulk of a helmet may not be suitable to the smaller cockpit of the aircraft. However, the CP stated that no formal risk assessment had been completed to support this decision. The operator reported that it issued each pilot (including the accident pilot) with company polo shirts made of 100% cotton as a measure of fire protection and the use of other protective clothing and helmets was left to individual pilots’ discretion. The CP indicated that some of their pilots did wear such items. It could not be determined if the accident pilot was wearing the company polo shirt. The ATSB noted that the operator’s job safety analysis (refer to section titled Job safety analysis) included consideration of protective equipment and clothing as methods of reducing risk factors.
The ATSB’s aviation medical specialist advised that if protective clothing and an appropriate helmet was worn, in most general circumstances, this would have reduced the severity of injury in an accident. However, they were unable to comment on the effectiveness of these items for this accident and noted that protective clothing and a helmet would not have prevented any smoke inhalation injury.
The International Airborne Geophysics Safety Association (IAGSA – refer to section titled International Airborne Geophysics Safety Association) recommended that appropriate clothing should be worn by all flight crew involved in geophysical surveys to minimise the immediate risk of fire in the event of an accident and for protection from exposure in a survival situation. These include:
cotton undergarments covered by long trousers and long‑sleeved shirt or an appropriate flying suit
closed shoes
have gloves available at all times
layers of clothing appropriate for the conditions
cold weather clothing should include felt lined boots, down parka with attached hood and large mittens.
IAGSA also recommended that for fixed‑wing operations, each individual operator should determine the appropriateness of the use of an industry approved helmet. A case by case, risk assessed approach should be adopted, taking into account the relevant variables for each specific survey task.
The Flight Safety Foundation’s Basic Aviation Risk Standard[9] is a set of risk‑based aviation industry standards. The standard covers a wide variety of aviation applications of which airborne geophysical survey operations were included. The standard implementation guidelines for survey operations also recommended appropriate clothing for crew such as non‑synthetic long trousers and pants or flying suit. It also recommended that helmets should be worn when operating below 500 ft AGL unless a risk assessment stated otherwise.
Flight following
Satellite tracking
Operator requirements
The operator had implemented flight following through use of the Spidertracks satellite tracking system installed on each of its aircraft. The company operations manual stated:
In addition to the required safety equipment the Company equips all aircraft with a real-time satellite monitoring system with a refresh rate of at least every 5 minutes and automatic alerting (to company mobile phone and email) in the event of an emergency.
Should the satellite monitoring system alert be inadvertently activated by the pilot an “ops normal” call should be made to the company as soon as practicable.
The ground operator assigned to each survey job was the primary person responsible for flight following. They were to monitor the aircraft’s location via the tracking system and initiate an emergency response, if required.
The morning pilot could not recall any specific pre‑flight requirements for the Spidertracks device and another company pilot reported that there were not any checks required, the device turned on once the aircraft’s electrical system was on.
The operations manual did not include flight following as a specific duty for the ground operator or any other staff member. Further, the manual did not detail procedures for the conduct of flight following, nor were there procedures or guidance to confirm that the tracking system was correctly configured and operating as expected prior to flight.
Automatic watch function
The operator was surprised that a Spidertracks automatic alert was not received during the accident and advised that, on a number of occasions, their satellite tracking had experienced dropouts. On some of those occasions, contact was made with the pilot and a system reset restored normal function. On other occasions, when contact with the pilot was not possible, the aircraft returned by the nominated estimated time of arrival (ETA). The operator had not contacted Spidertracks about the dropouts or conducted any other troubleshooting.
Spidertracks advised the ATSB that the automatic watch function on the aircraft’s device had not been activated on the accident flight, nor was it active for earlier flights on 2 and 3 March 2022. They further advised that there was no indication of any service‑related issues, confirming that up to the loss of data, the aircraft’s device was operating as expected. Diagnostic logs for the device were not available due to this data only being transmitted via mobile phone networks. Spidertracks confirmed that the length of time with no transmissions received, or a data loss or delay was not typical and could be indicative of a power or device failure, transmission interference or installation issue. Spidertracks found no recorded issues with the satellite service or their cloud platform at the time of, or leading up to, the accident.
Emergency response plan
The operator had a phased emergency response plan, predicated on an elapsed time since the aircraft’s ETA. Each phase was commensurate with an escalating level of concern. Satellite tracking was referred to in the plan, within the section Phase 1 - Uncertainty. Phase 1 commenced 0–15 minutes after the aircraft’s ETA had expired. The plan directed a check of the satellite tracking and if there was an abnormal or no indication in the system, the next step was to attempt contact with the crew. If contact with the crew was not possible and overall operations were assessed as not normal, the plan directed that the operations manager, as primary contact, to be notified, then the chief executive officer and CP as alternates.
The plan did not elaborate any further on required actions for an abnormal or no indication in the system prior to advancing to the next step, which was Phase 2 - Alert. Phase 2 commenced 15–30 minutes after the ETA had expired and directed the primary or alternate contacts to establish the final status of the aircraft via the tracking system. It included a note that, if there was no contact with company operations then the ground operator was to contact the Australian Maritime Safety Authority’s Joint Rescue Coordination Centre or local search and rescue services direct. Commencement of Phase 3 - Distress was at 30 minutes after ETA had expired or whenever the aircraft was confirmed as missing.
The operator commenced phase 3 at 1700, 30 minutes after the ETA for VH‑JVR had expired and then contacted the Joint Rescue Coordination Centre.
Emergency beacons
Emergency locator transmitter
The company operations manual stated that all company aircraft were to be fitted with an approved ELT or a portable ELT if the fixed device was inoperative or otherwise not serviceable. The operator was not able to determine why VH‑JVR was not fitted with an ELT.
The ATSB research report (AR‑2012‑128) discussed the potential safety benefits of an approved, fitted ELT, which were designed to automatically activate following an impact normally associated with a collision. While the research noted some limitations with the effectiveness of ELTs, the fitment of a crash‑activated ELT greatly increases the early notification for search and rescue efforts and arrival of potentially life‑saving medical treatment especially when occupants or crew are incapacitated.
Personal locator beacon
The CP and morning pilot stated that a personal locator beacon (PLB) was carried in the aircraft as part of a survival kit, which was secured to the passenger seat. The PLB was routinely carried in the aircraft, and not as an alternative to an ELT but as an additional item. In accordance with regulations, the PLB was classed as a survival ELT, and an alternative to a fixed ELT. However, the PLB was not identified in the wreckage and was likely consumed by fire.
The ATSB research report (AR‑2012‑128) suggested that carrying a PLB will most likely only be beneficial to safety if it is carried on the person, rather than being fixed or stowed elsewhere in the aircraft. The CASR Part 91 MOS stated that a survival ELT must be carried either on the person of a crew member, in or adjacent to a life raft, or adjacent to an emergency exit.
Operational information
Airborne geophysical survey flights
Airborne geophysical survey flights are conducted by a variety of rotary and fixed‑wing aircraft which have been specifically modified and equipped with geophysical sensors. Survey flights were normally flown below 500 ft AGL over the desired area via a pre‑determined pattern and at heights designed to maximise the quality of the data captured. The data provides a detailed below ground composition of the surveyed area, primarily to inform mining and resource industry activities.
Requirement for CASA low‑level rating
Operations requiring flight below 500 ft AGL, such as geophysical surveys, required a pilot to hold a CASA Part 61 low‑level rating. A low‑level rating is specific to various types of flying operations (such as aerial survey, firefighting or agricultural), however, the training and testing is not specific to any one type of operation. To obtain a low‑level rating a pilot must demonstrate competency in certain operational techniques, which included, but were not limited to, steep, maximum rate and minimum radius turns, procedure turns, recovery from approach to stalls (level and turning). In addition to holding a low‑level rating, MAGSPEC Aviation required prospective pilots to have a minimum of 500 hours as pilot in command. MAGSPEC Aviation then provides training specific to its operational requirements.
International Airborne Geophysics Safety Association (IAGSA)
The IAGSA is an international industry association comprised of airborne geophysical survey organisations with an overall objective to promote and enhance safety in the airborne geophysics survey industry. IAGSA publishes a safety manual for its member organisations, which details its standards and recommended safety practices.
IAGSA is a non-regulatory body and holds no authority to compel its members to follow its standards and recommended practices, which are not a replacement for the regulatory requirements that each individual organisation may operate under. However, members have agreed under the terms of membership to follow those standards and practices where they are more stringent or not covered by regulations, except where they have filed a notification of difference. Members are also required to complete an annual self‑audit. At the time of the accident, MAGSPEC Aviation’s most recent self‑audit outlined a number of differences to IAGSA standards and practices. Although IAGSA had requested it, it had not received a formal notification of differences from the operator.
Survey height
The operator was issued a CASA instrument in 2017, which allowed it to conduct operations at a height lower than that permitted by Civil Aviation Regulation (CAR) 157.[10] The instrument was last renewed in 2021 and was valid until 2024.
The instrument did not specify the lowest height that could be flown. The CP stated that survey flights would often be flown at 30 m (100 ft) AGL, although a standard or minimum height was not documented in the operations manual. Rather, the survey height would be requested by the client.
The CP explained that the requested survey height was assessed during the planning stage, through a review of maps of the survey area and the conduct of a reconnaissance flight. A detailed guide on how to conduct a reconnaissance flight was included as an appendix to the operations manual. This process would confirm if the survey could be flown at the requested height. The operator stated that, on numerous occasions this process resulted in the survey being flown at heights higher than requested.
The client for the accident survey specified a height of 25 m (82 ft) AGL.
The IAGSA safety manual acknowledged that there were increased risks associated with low flying and that operating at such heights can ‘aggravate the consequences of mechanical malfunctions or human error’. When discussing minimum safe survey heights, and while recognising that lower heights may improve the quality of survey data, they noted many differences of opinion among its members.
Having a predetermined height had been debated among the members, however, they concluded that ‘no single universal “minimum safe survey height” can be designated given the wide variety of survey conditions and aircraft characteristics’. As such, IAGSA indicated that the safety issue was not necessarily the survey height, but more importantly, could the survey be safely flown at the requested survey height. Consequently, IAGSA recommended that:
Clients specify the maximum clearance height possible, consistent with the objectives of the survey to be flown and that operators, prior to commencing a survey, conduct a detailed risk analysis in accordance with an internationally recognized procedure considering, but not limited to, the following factors and Appendix IV of this manual:
From the recorded data, the accident survey flight was flown in a back‑to‑back pattern, which was a series of consecutive parallel lines followed by a procedure turn used to establish the aircraft onto the next line in the reciprocal direction (Figure 6). This was the routine pattern used by the operator in its geophysical surveys. The client had specified 25 m spacing on east‑west survey lines.
The CP explained that procedure turns consisted of an initial climbing turn to establish the aircraft at about 300 ft AGL and about 400–500 m lateral offset from the next line. After this, a level turn would be commenced (into wind) at a 45–60° angle of bank (referred to as a steep turn) to intercept the next line. Descent to the survey height commenced once the aircraft wings were established straight-and-level.
Figure 6: Back-to-back pattern and procedure turns
Source: Aerial Application Association of Australia, annotated by the ATSB
IAGSA highlighted the risks associated with turns at low level:
Turns at low level present a considerable hazard, particularly if the terrain presents visual illusions; the aircraft descends in the turn, airspeed is low, or the angle of bank is steep. An excessive angle of bank, often resulting from close line spacing or drifting in strong crosswind conditions, is insidious as the stall speed of the aircraft increases with the angle of bank (assuming a level turn) whilst at the same time the aircraft’s speed is reduced from increased drag.
During straight and level flight there may be a significant margin above the stall speed, however in a steep turn the stall speed may be reached quickly with little warning and a stall in the turn at low level will likely result in a fatal accident.
For manoeuvring at low level, IAGSA recommended:
All turns at low level should be limited to a maximum angle of bank of 30 degrees and be done at a constant altitude. No climbs or descents should be carried out during the turn. If the terrain dictates that a climb is necessary the aircraft should be climbed to the required height prior to commencing the turn and any descent back to survey height should only be done after established in a wings level attitude.
The CP explained that the back‑to‑back pattern with procedure turns was the most efficient method and enabled the capture of higher quality survey data. They reported that flying consecutive lines was less workload intensive for their pilots, especially regarding obstacle hazard avoidance. This allowed a pilot to deal with a particular hazard for a short period as they moved away from it.
Operations manual – Special operations
Volume 2 of the operations manual, valid at the time of the accident, discussed aircraft operations and included a section titled Part 2D Special Operations specific to survey operations. It included sub sections on low flying, survey tolerances and safety considerations during surveys. However, there was limited detail with regard to the process or procedures for the conduct of low‑level survey flights.
As previously discussed, a standard or minimum survey height was not included in the operations manual.
In Part 2D1.1 Low Flying, height was discussed in terms of a minimum height when overflying occupied structures, vehicles or livestock but it did not include reference to other obstacles such as terrain, vegetation canopy or masts/antennas.
Part 2D1.4 Survey Tolerances stated:
Track, height and groundspeed tolerances for the survey will be established by the client and should be adhered to as closely as possible. Significant deviations will require the line to be re-flown.
Client established survey tolerances, although important to data accuracy, remain secondary to safety and pilots should disregard them as necessary to ensure the safety of aircraft, personnel, equipment, and environment.
Part 2D1.5 Safety considerations during survey, required a minimum survey speed to be established for each aircraft type operated by MAGSPEC Aviation. This was to be the greater of the 130% of clean stall speed (wing flaps up and landing gear up if retractable), 110% of the best single‑engine climb speed or 110% of the take‑off safety speed.
Although procedure turns and a back‑to‑back survey pattern were taught to, and routinely flown by all company pilots, the special operations section did not refer to these manoeuvres. The CP stated that there was no other reference document that outlined how the operator expected its pilots to conduct the procedure turns, nor were there any documented limitations such as a maximum angle of bank or minimum height AGL prior to commencing the procedure turn.
Aerodynamic stall
A wing generates lift as a result of the pressure differential created by airflow over the wing’s surface. The angle between the incoming or relative air flow and wing chord is known as the angle of attack (AoA). As the AoA increases, lift increases up to a certain angle, known as the critical AoA. At this point, the airflow over the upper surface of the wing becomes separated. This condition is referred to as an aerodynamic stall (or simply a stall) and results in a significant loss of lift and an increase in drag. Due to the sudden reduction in lift from the wing and rearward movement of the centre of lift, typically an uncommanded aircraft nose‑down pitch results.
A loss of altitude also occurs during the recovery from a stall and it is possible to stall with insufficient height above the ground to recover. The pilot’s operating handbook (POH) for the U206G stated that the maximum altitude loss during a stall recovery may be as much as 240 ft in power off conditions and straight and level flight. The U206G has a stall warning vane[11] and warning horn to alert the pilot of an impending stall.
Most general aviation aircraft typically have a critical AoA of around 16°. This critical AoA can be exceeded at any airspeed, any (pitch) attitude and any power setting. However, as most small aircraft are not fitted with an AoA indicator, the AoA at which the stall occurs may be referenced to an airspeed.
When banking or turning an aircraft, it is necessary to increase the amount of lift generated to ensure that the aircraft does not descend. This increases the AoA resulting in lift and drag greater than normal straight and level flight. This increases the load factor on the aircraft above 1 G. As the angle of bank increases, the lift required to maintain a constant altitude also increases, requiring the pilot to apply back pressure on the control column. The effect is, as the angle of bank and load factor increases, the stall speed increases. At 45° angle of bank, the load factor is 1.41. This results in an almost 19% increase in the wings level stall speed. At 60° angle of bank, the load factor is 2, resulting in an increase in stall speed of 41%.
The U206G POH provided the stall speeds at maximum weight with power off, flaps up, various angles of bank (up to the POH limit of 60°) and centre of gravity (CoG) positions (Table 2Table 2).
Table 2: U206G stall speeds (extracted from the POH)
Angle of bank
0°
30°
45°
60°
Stall speed (forward CoG)
55 kt
59 kt
65 kt
78 kt
Stall speed (rear CoG)
41 kt
44 kt
49 kt
58 kt
Recovery from a stall requires reducing the AoA by moving the control column forward, which normally means lowering the aircraft nose (pitching down).
Organisational and management information
MAGSPEC Aviation
MAGSPEC Aviation Pty Ltd commenced operations in 2017 to provide airborne geophysical survey services across Australia. It operated a fleet of 2 Cessna 206 and 2 Cessna 210 aircraft. At the time of the accident, they operated under a CASR Part 138 (aerial work) air operator’s certificate. Part 138 came into effect on 2 December 2021. Since commencing low‑level survey operations, the operator had experienced the following occurrences:
In 2018, the engine of a Cessna 210 failed necessitating a forced landing. The pilot was uninjured, however, the aircraft was substantially damaged. It was identified that sufficient fuel had not been transferred from the aircraft’s tip tanks to the main fuel tanks. The operator undertook action to review training and to reinforce fuel management procedures.
In 2019, a Cessna 210 struck a powerline and the aircraft sustained minor damage. The aircraft was safely flown back to its departure point. The operator reported that the aircraft had been flown on north‑south lines due to the sun’s position before transitioning to east‑west lines after the sun was no longer a factor. Following this, the pilot had flown 50 m from the powerline before making contact on the reciprocal heading. Subsequently, the operator incorporated a national database of powerlines into its pre‑survey assessment process.
In 2020, the engine of a Cessna U206G lost partial power and the pilot conducted a forced landing, resulting in substantial damage to the aircraft. The pilot was uninjured. Fuel starvation was determined as the reason for the engine power loss. It was identified that the aircraft had been operated with only one fuel tank selected instead of both. The operator updated checklists to incorporate the requirement for fuel tank selection to BOTH and amended the survey data acquisition system to provide periodic fuel check messages as a reminder to pilots.
Following the 2018 occurrence, the ATSB completed an occurrence brief (AB-2018-058). This was a short summary report and not an investigation, to allow for greater industry awareness of potential safety issues and possible safety actions. The ATSB did not investigate the other occurrences. CASA conducted 2 surveillance events following the 2018 occurrence. In response to the draft report, on 28 January 2025, the operator reported that they had requested assistance from CASA after the other occurrences but reported no assistance was provided. The ATSB reviewed CASA records, which indicated no action had been taken following the 2019 or 2020 occurrences (refer to section titled Regulatory oversight activity.
Safety management system
Managing safety
According to the International Civil Aviation Organization (ICAO, 2018), a safety management system is a systematic approach to managing safety that seeks to proactively mitigate risks before they result in an accident or incident. This includes defining the necessary organisational structures, accountabilities, responsibilities, policies and procedures.
At the time of the accident, there was no CASA regulatory requirement for the operator to have a safety management system. However, the operator had implemented a Health, Safety and Environmental Management System (HSEMS), for the purpose of describing:
…the process by which MAGSPEC aviation manages risks has been developed to meet the Civil Aviation Safety Authority SMS requirements in addition to providing more generalized guidance on the management of risk within the organisation.
Specifically, one of the operator’s policy commitments was to:
…minimize the risks associated with operational activity to a point that is as low as reasonably practicable/achievable…
While the HSEMS was submitted to CASA, a review of CASA records found that it had not been assessed, nor was there a requirement to do so.
Safety risk management
Risk management is a key component of safety management and includes hazard identification, safety risk assessment, safety risk mitigation and risk acceptance. It is an ongoing process as the aviation system is constantly changing, with new hazards introduced, and some hazards and associated risks changing over time (ICAO, 2018).
CASR Part 138 required an operator conducting aerial work to undertake risk assessments of its operations. This was a new requirement introduced with Part 138. The Part 138 MOS detailed a layered approach to risk assessment and that before conducting an operation:
(a) the operator’s operations manual must contain:
(i) pre-operational risk procedures [refer below] for risk assessments and mitigation processes applicable to the operation; and
(ii) procedures for post-flight risk review; and
(b) the operator must have a flight risk management plan based on a pre-operational risk assessment in accordance with the procedures; and
(c) the operator must ensure that the operator and each crew member is satisfied, in a pre-flight risk review, that the flight risk management plan will eliminate, reduce or mitigate risks and hazards to the extent that it is safe to conduct, and continue, the operation without unacceptable risk to the crew members, any aerial work passengers, the aircraft or any other person or property.
The MOS further specified what was to be included in an operator’s pre‑operational risk procedures:
a. processes for identifying, reporting and recording hazards;
b. processes for analysing identified hazards and assessing the risks they may pose, including for pre-flight, in-flight and post-flight stages of operations;
c. processes to mitigate the risks or control the risks, including processes for the incorporation of risk controls into standard operating procedures;
d. the creation and management of:
i. a risk register; and
ii. records of dedicated risk assessments performed to address each type aerial work operation that is to be conducted, including details of the risk assessors;
e. procedures to ensure that the pilot in command and the other crew members are familiar with the pre-operational risk assessment and the associated standard operating procedures (SOP);
f. in-flight procedures for the pilot in command and the other crew members to consider and manage the risks associated with aerial work operations.
The operator’s HSEMS stated that safety risk management begins with hazard identification and then assessing the risks associated with the hazard in terms of likelihood and severity. The manual further stated that, once the level of risk was identified, appropriate remedial or mitigation measures could be implemented to reduce the risk to as low as reasonably practicable. The risk management process detailed in the HSEMS followed a 5‑stage process:
Stage 1 - Identify the hazard and associated risks
Stage 2 - Assess the risk in regard to severity and likelihood
Stage 3 - Evaluate risk tolerability
Stage 4 - Treat/mitigate the risk
Stage 5 - Monitoring
Stage 1 of the process listed sources for hazard identification and stated that the safety manager was to use the Donesafe[12] system to manage and record these hazards. It also noted that:
Due to the varying nature of MAGSPEC Aviation’s operating environment a separate Operational Job Safety Analysis (JSA) (see appendix 3) was undertaken by the Chief Pilot or his designee to assess site-specific risks prior to each job provide an overall risk rating for the job.
Where non-site-specific items are identified as part the JSA or field crew safety meeting these will be reported to the HSEMS system via the DONESAFE “Hazards” report tab.
Each survey task, including the risks associated with that task, were assessed via the job safety analysis (JSA). Any risks identified in the JSA that were not specific to the survey tasking location were entered into the Donesafe system. The risks specific to the location were not captured in the system.
Pre-operational risk assessment
One of the key requirements for managing risk was that an operator should undertake an overarching assessment (pre‑operational risk assessment) to consider and evaluate the risks associated with its proposed operations, in this case, low‑level geophysical survey. This assessment recognised the underlying principles of CASR Part 138, where the risks and hazards associated with a type of aerial work operation are common to that type of operation. The matters to be considered in the assessment included, but were not limited to the (CASA, 2023):
− nature of the intended operation and its particular characteristics
− location (if known) of the intended operation and its particular characteristics
− aircraft to be used in the intended operation and their performance profile and impacts of serviceability status
− qualifications and experience of the FCMs [flight crew members] and support personnel to be used in the intended operation
− generic or known hazards particular to the type of aerial work operation, external to the aircraft, that may be met during the operation.
CASA advisory circular 138‑05 v2.1 Aerial work risk management, stated that an operator should use data from the risk register and dedicated risk assessments to inform the pre‑operational risk assessment. Once populated, the assessment should then be updated over time and from operational experience, to incorporate lessons learnt from previous operations. Further, to ensure it is readily available to all crew members, it should form part of the company’s operations manual.
The ATSB’s review of the HSEMS and operations manual did not identify any requirement for a pre‑operational risk assessment to be completed.The CP also confirmed that, at the time of the accident, such an assessment had not been conducted.
Risk register
Safety risk management activities should be documented, including any assumptions underlying a risk assessment, decisions made, and risk controls implemented. A risk register could be used to ensure identified hazards and risks that emerged during planning or day‑to‑day operations were tracked and mitigated as part of formal risk management processes. An operator’s risk register can also be incorporated into the pre‑operational risk assessment. The register could include the hazard, potential likelihood and consequences, assessment of the associated risks, when or where it applied, and any controls put in place to mitigate the risk. Notably, (ICAO, 2018):
Maintaining a register of identified hazards minimizes the likelihood that the organization will lose sight of its known hazards. When hazards are identified, they can be compared with the known hazards in the register to see if the hazard has already been registered, and what action(s) were taken to mitigate it.
The CP reported that a risk register was not maintained for the company’s operations. Although it was noted that the operator did retain a fatigue risk register.
Flight risk management plan
The results of the pre‑operational risk assessment were to be considered when preparing a flight risk management plan, which was specific to an individual flight or task within the type of operation. The plan should outline the specific mitigators or risk controls that were to be used during the flights. The flight crew should also have sufficient time to review and confirm the plan prior to the commencement of the operation.
Job safety analysis
Components
As required by the company operation’s manual, the JSA was the documented risk management process designed to address the safety concerns with each project the operator conducted, that is, for each specific survey task. The ATSB’s interpretation of the Part 138 risk assessment requirements was that the JSA was equivalent to the flight risk management plan, as discussed above. The JSA consisted of 5 parts:
Part A - Pre-survey risk assessment: This assessment was to be completed by the operations manager at the time a tasking was quoted and included details on the activity, hazards, hazard effects, initial risk score, risk mitigators, residual risk, and a final risk score. This used a pre‑populated risk matrix with 14 hazard areas, each of which were assigned a descriptor and risk score of 1 (negligible) to 5 (unacceptable). The total risk score determined if any further action was required, such as a need for additional risk controls or stopping the tasking until the risk was reduced.
Part B - Operational job safety analysis. This was to be completed by the CP or other suitable person prior to commencing the survey task. This considered any operational limitations relating to aircraft performance, obstacles and human performance, whether any hazards affected the safety or technical performance of the survey, and if any changes were required. The risk level for the task was assessed using a pre-populated matrix with 27 hazards, but with instructions to add more as appropriate. The final risk level determined if the survey could proceed as planned (low risk), or if the survey could proceed with approval from the CP and amendments to the plan or additional risk mitigators (medium risk), or if the survey was not to proceed as currently planned (high risk).
Part C - Field crew safety meeting: The meeting was to be completed by operational personnel at the survey site, prior to commencing survey operations and every crew change. This section was a yes/no answer sheet covering a range of operational areas designed to assess any additional hazards and risks not identified in Parts A and B. At the direction of the CP, a reconnaissance flight could also be performed to assess the survey area for any additional risks or hazards not already identified in the original JSA.
Part D - Post-survey field crew meeting: This meeting allowed the operator to better understand any issues faced on the job and if anything needed to be accounted for, either at that specific location or for an ongoing basis.
Part E - Emergency response plan: This plan was to be reviewed during the field crew safety meeting and crew members were to ensure that the contact and procedure details were correct.
Neither Part A nor Part B referred to consideration of previous JSAs for any applicable risk information that may be relevant to the current JSA.
Survey task assessment
Parts A-C of the JSA completed for the accident flight survey task are discussed in the following paragraphs.
Part A was completed by the operations manager and listed hazards including the 25 m survey height, which was assessed with the highest risk score of 5. It did include mitigating factors of carrying a portable personal ELB and portable GPS, conducting operations with satellite flight following and a comprehensive pilot briefing including maps.
Several elevated risk areas were identified on the matrix, such as operations below 100 ft AGL and operating in hot conditions between 35–40 °C. Overall, the initial risk rating for the survey task was determined to be low, based on a score of 36 (Figure 7)Figure 8.
Figure 7: Part A – Initial pre-survey risk assessment for the accident task
Source: MAGSPEC Aviation, annotated by the ATSB
The CP and operations manager approved Part B of the JSA, identifying that the survey height and antenna/masts, and the survey location with regard to other aircraft activity were concerns. When considering if there were any hazards that would affect safety or the technical performance of the survey, the survey height of 25 m was noted, and the possibility of trees, powerlines and masts in the area were low still but still a risk. As such, it was determined that a detailed reconnaissance flight was to be conducted.
The final risk level was assessed as low, with 4 hazards identified (Figure 8Figure 9). The ATSB noted that the hazard of ‘terrain clearance less than 30 metres’ had not been ticked. However, if it had been selected, the final risk level would have remained at low.
Figure 8: Part B – Hazards risk matrix for the accident tasking
Source: MAGSPEC Aviation
Part C had been originally completed by another pilot and the ground operator. That pilot had conducted a reconnaissance flight of the survey area and signed part C noting that no additional risks had been identified. That pilot was subsequently assigned to another task.
The ATSB noted that the survey height was referred to in the question, Can the job be flown at the suggested survey height? and this was answered as yes with no amplifying comments.
The day prior to the accident, the ground operator met with the accident and morning pilot to conduct another field crew safety meeting. They discussed the JSA, and the ground operator reported that they advised the pilots about some taller trees in the area, which had been identified in the reconnaissance flight (but not noted in Part C).
Text messages between the accident pilot and CP showed that conducting another reconnaissance flight was discussed. The CP suggested that another could be done if the pilot felt it was required but there was no direction from the CP to do so. The morning pilot completed another reconnaissance of the survey area prior to commencing their survey.
In reference to the utility and sufficiency of the JSA, the operator advised on 28 January 2025 in response to the draft report that they considered the JSA to be their risk assessment process and was a combined risk register, pre‑operational risk assessment, flight risk management plan and record of the crew meeting. The operator further advised that the JSA was reviewed by CASA during the transition to Part 138 and:
This risk assessment was approved by CASA during the 2nd December 2021, Part 91 / 138 AWK [aerial work] changes. It has been accepted and approved by multiple third-parties, including those that represent BARS [Flight Safety Foundation’s Basic Aviation Risk Standard].
The ATSB sought clarification from CASA to determine if the JSA met the requirement of Part 138 and whether it had been approved by CASA. On 1 May 2025, CASA advised:
The JSA as described in the report does not meet the requirement of a pre-operational risk assessment.
The reasons for this advice are:
• The ATSB report outlined that Part A of the JSA had a pre-populated risk matrix with 14 hazard areas and Part B of the JAS had a pre‑populated matrix with 27 hazards and instructions to add more as necessary.
• CASA’s AC 138-05 identifies how a risk register is a critical component to the creation of a pre‑operational risk assessment and CASA notes that the ATSB report mentions that the operator’s Chief Pilot (CP) “reported that a risk register was not maintained for the company’s operations” which supports that a pre-operational risk assessment was not produced.
• CASA agrees with the ATSB that this activity is not specifically considering or evaluating the risks associated with the type of aerial work operation to be conducted, i.e. the JSA process is basically done on a per task basis, which is not the same as the pre-operational risk assessment as the pre‑operational risk assessment is intended to be an enduring document that is regularly updated from risk register updates and post-flight risk reviews (see the first sentence of CASA AC 138‑05 paragraph 4.2.5).
• Effectively, the JSA Part A is potentially covering elements of risk assessments that would support the updating of the pre-operational risk assessment but is not creating the pre-operational risk assessment itself.
• CASA further advised:
• The accident occurred 3 months after the commencement of the new flight operations regulations, of which Part 138 of CASR and its supporting Manual of Standards was one element.
• Under the transitional rules in Subpart 202.EAA of CASR, holders of AOCs authorising aerial work under the pre-2 December 2021 paragraph 206(1)(a) of CAR, where the AOC was in force immediately before 2 December 2021, had these AOCs recognised as legally being an aerial work certificate and such operators were required to ensure their operations manuals complied with Part 138 of CASR and contained all necessary content to enable that compliance.
• As the operator was the holder of an AOC authorising aerial work under the pre-2 December 2021 rules, the content of their operations manual would have been approved by CASA as part of them holding that AOC. Compliance with the new flight operations regulations for all such operators would be reviewed at the next appropriate CASA oversight event.
Regulatory oversight activity
Regulatory framework
CASA was responsible, under the provisions of Section 9 of the Civil Aviation Act 1988, for the safety regulation of civil aviation in Australia and of Australian aircraft outside of Australia. Section 9(1) stated the means of conducting the regulation included:
(c) developing and promulgating appropriate, clear and concise aviation safety standards;
(d) developing effective enforcement strategies to secure compliance with aviation safety standards…
(e) issuing certificates, licences, registrations and permits;
(f) conducting comprehensive aviation industry surveillance, including assessment of safety‑related decisions taken by industry management at all levels for their impact on aviation safety…
The 2 primary means of oversighting a specific operator’s aviation activities were:
assessing applications for the issue of, or variations to its air operator’s certificate (AOC) and associated approvals (including approvals of key personnel)
conducting surveillance of its activities.
CASA was required by Section 28 of the Civil Aviation Act 1988 to satisfy itself about various matters when processing an application for the issue of, or variation to, an AOC. The matters included whether the organisation was suitable and whether it had suitable procedures and practices to ensure that AOC operations were conducted safely.
CASA provided records related to their assessment of MAGSPEC Aviation’s initial AOC and low flying applications.
Initial issue of air operator’s certificate
The CASA entry control process involved assessing an application for the issue of a new AOC or a variation to an existing AOC. The worksheet used by CASA for an AOC assessment was intended to be used in conjunction with the AOC Process Manual, AOC Handbook, other relevant technical assessor handbooks and applicable legislation. This worksheet contained the criteria required for an assessor to undertake a technical assessment. It focused on generic regulatory requirements applicable to most operators and there was no specific criteria that referred to assessing an operator’s primary activity, in this case, low‑level survey operations. Although the assessment process confirmed that the operator had processes and procedures to support its operations, there was no evidence that these were examined in any detail for their suitability for the proposed operations.
However, the CASA officer processing the AOC application acknowledged that, while it was a new operation, the organisation included personnel from a previous operator, and that these personnel had experience and exposure to low‑level survey operations. The officer further stated that this experience was evident during the assessment, interview, and inspection phases of the assessment.
As part of the AOC application, CASA was to also approve the appointment of the CP. The CP’s records included an assessment paper, interview record, and notes from an assessment flight. The assessment focused on the CP’s ability to manage the regulatory requirements of an AOC holder, yet did not indicate how the operator would conduct its low‑level survey operations. The assessment flight did not include any low‑level flying as CASA did not permit its officers to undertake low flying.
The AOC was issued to the operator on 3 October 2017.
In December 2021, CASA amended its AOC entry control procedures to include more emphasis on assessing the proposed primary activity. A specific worksheet was introduced for assessing a Part 138 application and included reviewing the processes that allow an operator to safely conduct and manage its aerial work operation in compliance with the regulations.
Low flying approval
The AOC Handbook acknowledged that low flying was an operational requirement and that an application for low flying under CAR 157(4)(b) was required. This assessment was conducted at the same time as the initial AOC application.
The worksheet for the AOC application did not record any assessment undertaken by CASA to approve the operator to undertake low flying below the levels permitted in CAR 157. However, the assessing officer indicated that a key component of issuing the low flying approval was that the operator had a legitimate requirement and that its CP and line pilots held the required low‑level rating. There was no record of any in depth assessment of how the operator would address the risks associated with low flying. Further, the AOC Handbook did not provide any guidance or instruction on how such an application should be assessed.
The low flying instrument was issued to the operator on 22 September 2017.
Surveillance post‑AOC issue (pre‑accident)
Post‑authorisation review
As at 2017, following the issue of an initial AOC, CASA was to conduct a post‑authorisation review (PAR) of the operator to ensure that all the entry control requirements were being met. This surveillance activity was to be conducted within 6–15 months following the initial issue.[13] As described in the CASA Surveillance Manual, a PAR was a type of level 1 surveillance, which was a structured, forward planned larger surveillance event.
The CASA records showed that a PAR, as defined in its surveillance manual, had not been undertaken on the operator.
In response to the draft report on 3 February 2025, CASA advised the ATSB that:
At the time of the accident CASA conducted its surveillance planning under the National Surveillance Selection Process (NSSP), which was a risk-based methodology for the selection and prioritisation of surveillance events. Under the NSSP an operator such as this did not require a post authorisation review. CASA has since implemented a multi-year surveillance approach whereby all Aerial Work Operators undergo surveillance on a regular basis, irrespective of the degree of risk that CASA has assessed. This multi-year surveillance approach is one of many core elements of CASA’s National Oversight Plan.
On 3 April 2025, the ATSB and CASA had a follow‑up briefing to seek clarification on its responses to the draft report. CASA advised that the obligation for a PAR could also be achieved through an alternative activity, and in this case had been accomplished through the conduct of a level 2 surveillance event. CASA indicated that the level 2 surveillance, conducted in July 2018 (discussed below), was noted in its surveillance system as ‘post authorisation’ and would likely have been similarly scoped to a PAR. Therefore, this was considered an equivalent activity at the time. CASA had not provided the ATSB any supporting documentation indicating that an equivalent activity was permitted, or what should have been considered if this was to be undertaken.
Surveillance in 2018
A level 2 surveillance event was a less formal interaction with an operator and could be in the form of checklist-based compliance and product checks of a specific section of its systems. A level 2 surveillance event took place in July 2018, after the operator’s first occurrence. The planned scope included airworthiness assurance, fuel load control, operational standards, and safety assurance. Nil findings were issued, and the CASA surveillance team noted that the operator was still in the process of reviewing its operating procedures with changes to be reviewed at the next surveillance event scheduled for later in 2018. It was not evident to what extent that low‑level survey operations were examined.
A second level 2 surveillance took place in October–November 2018. The planned scope included the same areas as the previous surveillance with the additional items of:
airworthiness control
implementation of the drug and alcohol management plan
crew scheduling
flight systems
safety risk management
assessments
training infrastructure
training management.
Three safety findings and 7 safety observations were issued as a result of that surveillance. The surveillance team noted that the operator was actively trying to mitigate some of the operational risks, but the operations manual was lacking some of the procedures followed by the operator. The findings related to non‑conformance with operations manual procedures, uncontrolled documents, and aircraft defect management.
Observations were not required to be actioned by the operator, although CASA did encourage them to do so. One observation related to fuel load control and procedures for addressing discrepancies in fuel quantity. Another observation related to limited procedures for the completion of the JSA. The surveillance report did not make any findings or observations on overall processes or procedures for low‑level survey operations.
Periodic assessment tool
The authorisation holder performance indicator (AHPI) was a questionnaire‑based tool used by CASA to assess ‘the apparent risk to safety presented by an authorisation holder [operator]’. The AHPI tool consisted of a number of factors and sub‑factors associated with organisational characteristics and performance, commonly thought to affect or relate to safety performance behaviour. This was used by CASA to assist with determining whether any risk‑based surveillance of an organisation was required, and to scope the areas for that assessment.
A number of AHPI assessments had been completed by CASA and 5 out of the 6 AHPIs did not trigger any higher priority for surveillance. The last AHPI prior to the accident was completed in February 2022. CASA noted that there was no record in its system of a formal PAR being conducted, and there was no record of action following the 2019 and 2020 occurrences. The CASA officer recommended surveillance take place at the earliest possible convenience.
Transition to Part 138 regulations
In response to the draft report, on 1 May 2025, CASA advised the ATSB that the accident occurred about 3 months after the commencement of the new flight operations regulations, which included Part 138. Under the transitional arrangements to the new regulations, current holders of an AOC authorising aerial work before 2 December 2021 had this certificate legally recognised as being an ‘aerial work certificate’. These operators were required to ensure that the operations manual complied with Part 138 and contained all the necessary content to enable that compliance.
In this case, as the operator held an AOC prior to 2 December 2021, the content of its operations manual would have been approved by CASA. The operator’s compliance with Part 138 was to be reviewed at the next appropriate CASA oversight event.
While operators were not required to submit their entire operations manual for assessment prior to 2 December 2021, as part of the transition, CASA required operators (no later than 60 days prior) to submit extracts from their operations manual covering 2 key measures. These included change management and procedures for the carriage of aerial work passengers required under Part 138. CASA only required operators to submit their entire updated operations manual immediately before the commencement date of the new regulations.
On 27 September 2021, MAGSPEC provided CASA with its complete operations manual, the HSEMS, including the change management and carriage of aerial work passenger procedures. CASA notified MAGSPEC via email in April 2022 that its initial submissions related to these 2 aspects were not yet compliant. Following a further submission by the operator, on 18 August 2022 CASA advised via email that these areas were ‘compliant’. CASA did not provide any advice related to an assessment of any other parts of the operations manual including those related to operational risk management.
Surveillance post-accident
Shortly after the accident, CASA conducted an initial review to determine if further surveillance of the operator was required. The CASA officer noted that the operator had never undergone a level 1 surveillance event or had a PAR conducted. The officer recommended that a response surveillance event should be scheduled.
On 31 August 2023, the ATSB briefed CASA on the draft investigation findings, which included discussion on the operator’s risk management processes in place at the time of the accident. A similar briefing had also been provided to the operator on 19 July 2023. CASA completed a level 1 systems audit of the operator in September 2023. This level of surveillance is a structured, larger-type event that considers the specific activities conducted by the operator. The audit included a review and follow-up of this accident. The scope included:
airworthiness and maintenance aspects
aircraft and passenger loading control
crew scheduling and fatigue management
operational standards, and data and documentation
authorised activities
flight systems and operational support systems
safety assurance and safety risk management.
The audit identified 6 safety findings and one observation for the operator related to maintenance documentation, fatigue management, and operations manual compliance. Specifically, one finding regarding the operations manual noted that it did not include all the content as required by the regulations. This included limited detail regarding:
processes and procedures relating to low‑level operations and manoeuvring and role specific equipment usage (data acquisition system)
processes and procedures relating to the training of operational and handling procedures with regards to low‑level operations and manoeuvring and role specific equipment usage (data acquisition system).
There were no other findings or observations made regarding the operational risk management processes and procedures.
At the time of the audit, the operator advised CASA that it was waiting for the completion of the ATSB’s investigation prior to initiating any changes to its processes or procedures. However, it was noted that, while the audit was not an investigation, a number of potential latent issues existed, including:
• No active or consistent fatigue monitoring of flight crew during operations other than the required recording of flight and duty records.
• Limited detail in operational risk assessments pertaining to operations in general and the additional fatigue obligations as required by legislation.
• Limited documented operational procedures and associated training relating to low level flight techniques and procedures including the use of operational equipment utilised during survey operations [as detailed above].
• Limited documented process and procedure, and subsequent detail established when conducting internal investigation following operational incidents.
Similar occurrences
Regulatory oversight
Regulatory oversight of air operations has been discussed in detail in previous ATSB investigation reports. These included a fatal Cessna 172 accident at Agnes Waters, Queensland in 2017 (AO‑2017‑005), a fatal Eurocopter EC120B helicopter accident at Hardy Reef, Queensland in 2018 (AO‑2018‑026), and a fatal Eurocopter EC135 helicopter accident at Port Hedland, Western Australia in 2018 (AO‑2018‑022).
These investigations identified that CASA’s regulatory oversight activities had not specifically examined the nature of the operator’s primary activities. The findings were as follows:
The Civil Aviation Safety Authority’s procedures and guidance for scoping a surveillance event included several important aspects, but it did not formally include the nature of the operator’s activities, the inherent threats or hazards associated with those activities, and the risk controls that were important for managing those threats or hazards. (safety issue AO-2017-005-SI-08)
Although the operator’s primary helicopter activity was conducting charter flights to pontoons at Hardy Reef, regulatory oversight activity by the Civil Aviation Safety Authority had not specifically examined the operator’s procedures and practices for conducting operations to these helicopter landing sites.
Although the operator’s primary helicopter activity was conducting marine pilot transfers, regulatory oversight activity by the Civil Aviation Safety Authority had not specifically examined the operator’s procedures and practices for conducting approaches and landings to ships at night in degraded visual cueing environments.
In response to safety issue AO-2017-005-SI-08, CASA amended its surveillance and scoping form to require consideration of current activities. Further, it proposed the addition of an operator profile report to provide current, contextual information on an operator with a view to provide a more effective audit scoping process in which consideration and documentation of an operator’s activities was mandatory.
In response to the draft report, on 3 February 2025, CASA advised the ATSB that:
CASA’s Surveillance activities do not include specific checks of the suitability or effectiveness of the processes and procedures in these specific areas. However, under CASR [Civil Aviation Safety Regulation] Part 138.370, the operator is required to conduct risk assessments and mitigation processes before conducting any particular aerial work operation (that is, they must consider the risk of the specific operation and introduce appropriate mitigants). Surveillance is carried out under set scope of 138 operators under this regulation to ensure the operations are suitably risk assessed.
Based on the actions in response to AO-2017-005-SI-08, the ATSB was of the understanding that an operator’s primary activity was considered in entry control processes and surveillance scope. As such, the above comment was also discussed at the ATSB‑CASA meeting on 3 April 2025. CASA advised that an operator’s primary activity is considered, and when assessing a Part 138 operator it uses a standardised worksheet to ensure there is a consistent approach to that assessment and to maintain a record of the decision‑making process.
Low-level accidents
There has been a number of ATSB investigations into fatal accidents that resulted from a loss of control at low altitude, from which a recovery was not possible.
On 29 April 2012, the owner-pilot of a Cessna 150 aircraft, registered VH‑UWR, was aerial stock mustering on a cattle station about 55 km north‑east of Bourke, New South Wales. The aircraft was observed circling over an area (where cattle were not moving), then entered a steep descent followed by the sound of an impact. The aircraft was substantially damaged, and the pilot sustained fatal injuries.
The ATSB found that, while manoeuvring at low level, the pilot inadvertently allowed the aircraft to aerodynamically stall, resulting in a high rate of descent and collision with terrain. There was insufficient information about pilot control inputs to establish the factors that precipitated the stall.
On 29 December 2014, a Cessna 172S aircraft, registered VH‑PFT, departed Cambridge Airport, Tasmania to photograph yachts participating in the 2014 Sydney Hobart race. On board the aircraft were the pilot and a photographer.
At about 1815 local time, the aircraft commenced low-level photographic runs on yachts to the east of Cape Raoul. Shortly after completing a run on one yacht at a height of about 50 ft, the aircraft entered a steep climbing turn. The aircraft had almost completed a 180° turn when the upper (right) wing dropped sharply while the aircraft’s nose pitched down to almost vertical. The aircraft impacted the water’s surface in an almost vertical nose‑down attitude with wings about level. Both aircraft occupants were fatally injured, and the aircraft was substantially damaged.
As a result of the steep climbing turn, the aircraft’s upper wing aerodynamically stalled, resulting in a rapid rotation out of the turn. The steep pitch attitude indicated that, due to the stalled upper wing, the aircraft entered a spin. There was insufficient height for the pilot to recover the aircraft.
On 13 April 2021, a Cessna R172K aircraft, registered VH-DLA, departed Canberra Airport, Australian Capital Territory, with a pilot and an observer on board to conduct powerline survey work to the north of Sutton township, New South Wales.
About 3 hours into the flight, while conducting a powerline inspection in the vicinity of Tallagandra Lane, nearby witnesses observed the aircraft flying low above the trees before commencing a left turn that continued into a steep descent and collision with terrain. The pilot and observer were fatally injured, and the aircraft was destroyed.
The ATSB found that, while manoeuvring to align the aircraft to inspect a powerline, the aircraft aerodynamically stalled and entered a spin at a height that was insufficient for recovery prior to the collision with terrain.
On 4 December 2021, the pilot of an Air Tractor AT‑400 aircraft, registered VH‑ACQ, was conducting aerial spraying operations on a property 75 km west‑south‑west of Moree, New South Wales.
At 0632 local time, the aircraft took off from the property’s airstrip with the first spray load. The pilot then completed 10 spray loads, each time returning to the airstrip to replenish its load.
Prior to departing with the 11th load, the aircraft was refuelled to full and its spray load refilled. The aircraft then returned to the western side of the target block, but after descending to recommence spraying towards the south, the aircraft climbed and turned away to track north and overfly a flood-affected area. The pilot radioed the company operations manager expressing concern about the weather conditions and the potential for chemical to drift onto a neighbouring property. About 5 minutes later, the aircraft returned to the target block, this time on the eastern boundary.
The pilot then conducted 2 ‘smoker’ runs to assess the drift, followed by 5 back‑to‑back (parallel) spray runs. At the end of the 5th spray run, the aircraft was observed to climb then enter a right procedure turn. During the turn, the aircraft descended rapidly, collided with terrain, and was subsequently destroyed by fire. The pilot sustained fatal injuries.
The ATSB found that the aircraft was too close to the start of the spray run during the turn, which probably resulted in the pilot tightening the turn. This almost certainly resulted in an aerodynamic stall at a height too low to recover before colliding with the ground.
Safety analysis
Introduction
In the afternoon of 3 March 2022, a Cessna U206G, registered VH‑JVR, was being operated on a low‑level geophysical survey flight. When on the 25th survey line, the aircraft collided with terrain and was destroyed in the post‑impact fire. The pilot was fatally injured.
This analysis will discuss the potential reasons for the loss of control and the initiation of the emergency response. The angle of bank regularly used for procedure turns, and the benefits of protective clothing and helmets are also examined. It will also consider the operator’s risk management processes and supporting procedures for low‑level geophysical survey flights, and regulatory oversight of these activities.
Loss of control
The last recorded position of the aircraft was on a survey line consistent with the planned survey parameters. Likewise, a comparison of the available flight data indicated that the aircraft’s location was in a similar position to that of previous procedure turns. Therefore, it was likely that the aircraft was being manoeuvred onto the next survey line at the time of the accident.
The wreckage examination determined that the aircraft impacted the trees in a left angle of bank, with a steep angle of impact and a nose‑down attitude, indicative of a loss of control. The ATSB considered several reasons for the loss of control. There was no evidence to suggest any airborne impact with a bird nor that the weather conditions affected the pilot’s ability to maintain control of the aircraft. To the extent possible, the ATSB determined that the aircraft was structurally intact, there was no flight control malfunction, and the engine was producing power at the time of impact. Further, the pilot did not have any reported health issues, and the post‑mortem and toxicology examinations did not identify the presence of any natural disease or substances. While some causes of incapacitation may not always be identified post‑mortem, there was no evidence to suggest that the pilot had become incapacitated during flight.
The pilot had previously conducted 24 survey lines with no apparent issues identified from the recorded data. Based on the ATSB’s analysis, the aircraft’s airspeed had remained above the aerodynamic stall speed during the procedure turns. Therefore, there was no indication of a near or actual stall on the previous turns. Although, the data identified that the procedure turns were consistently conducted at heights below which a recovery from a stall and loss of control may not be possible. A stall situation was a plausible explanation, as found in previous ATSB investigations into low‑level accidents. However, in this case, this remained only a possibility due to the lack of recorded data beyond the last known position and no witness observations, making it difficult to determine the precise circumstances that led to the loss of control and collision with terrain.
Contributing factor
It was likely that, during a manoeuvre to intercept the next survey line, for undetermined reasons, control of the aircraft was lost at a height from which recovery was not possible, resulting in a collision with terrain.
Delayed emergency response
The operator had a phased emergency response plan, predicated on an elapsed time since the aircraft’s estimated time of arrival (ETA). Each phase was commensurate with an escalating level of concern. Unless there was a notification of an accident by other means, the distress phase would commence at 30 minutes past the ETA, at which point the Joint Rescue Coordination Centre (JRCC) would be contacted to initiate search and rescue activity. Each phase of the plan required accessing the satellite tracking system to ascertain the location of the aircraft.
When the satellite tracking data stopped at 1343, the automatic watch function did not send an alert to the operator after 15 minutes had elapsed, as this function had not been activated. This was not noticed until 1430 when the ground operator conducted a periodic check. While the operator reported previously experiencing dropouts of the satellite tracking system, Spidertracks confirmed that up to the loss of data, the device was functioning as expected and that there were no recorded system outages.
The ground operator was not able to contact the pilot via mobile phone and there was no emergency beacon activation. The ATSB noted that, while the aircraft was not fitted with an emergency locator transmitter, a personal locator beacon was carried in the aircraft. However, as this was not worn by the pilot, this was not readily accessible following the accident.
As such, the status of the pilot and aircraft could not be established. The operations manager then advised the ground operator to follow the emergency response plan and wait until the ETA. When the aircraft did not arrive at the ETA of 1630, about 3 hours after the accident, in accordance with the plan the operator contacted the JRCC at 1701.
The JRCC promptly initiated search and rescue procedures, and an aircraft departed at 1739 and located the aircraft wreckage at 1852. A search and rescue helicopter crew physically located the pilot at 0042. With the time taken to access the pilot, whose injuries required immediate medical care, it was very likely that even if the search and rescue activities had commenced when the satellite tracking data was lost, the pilot would have succumbed to the injuries received.
When an accident occurs and any injuries that result are potentially survivable, a timely response is essential. Minimising the time for search and rescue and enabling emergency services to respond as quickly as possible may increase the chances of a successful outcome.
Other factor that increased risk
An emergency response was not initiated until 30 minutes after the aircraft's estimated time of arrival, which was 3 hours after satellite tracking had stopped and attempts to contact the pilot had been unsuccessful. Although an earlier response was very unlikely to have altered the outcome in this case, minimising the time for search and rescue and enabling emergency services to respond as quickly as possible may increase the chances of a successful outcome.
Low-level manoeuvring
The operator’s pilots routinely used high angle of bank procedure turns to manoeuvre between consecutive survey lines. This back‑to‑back pattern was described by the chief pilot (CP) as the most efficient method and it also reduced pilot workload, especially for obstacle and hazard avoidance.
The CP stated that procedure turns were trained to be at about 300 ft above ground level and a 45–60° angle of bank (known as a steep turn). Analysis of the accident flight indicated that the pilot was flying high angle of bank procedure turns consistent with the operator’s training. However, they were turning at an average of about 200 ft, lower than what was explained by the CP.
The ATSB noted that, during the preceding 24 turns, the pilot had maintained sufficient margin above the stall speeds listed in the pilot’s operating handbook. However, as aircraft data was not available up to the loss of control it was not possible to determine if the aircraft stalled nor the exact circumstances that existed.
The similar occurrences discussed involved a loss of control that was preceded by a stall at very low heights. The U206G pilot’s operating handbook stated that up to 240 ft may be required to recover from a stall, but this height was based on flight testing in controlled conditions and that significantly more height may be required.
High angle of bank turns at low level present a significant risk and International Airborne Geophysics Safety Association (IAGSA) recommended that the angle of bank should be limited due to the stall speed increasing with increasing angles of bank, thus reducing the safety margins available. These margins can be quickly eroded if a pilot tightens the turn to ensure they intercept the survey line, which can increase the load factor further, resulting in reaching the stall speed quicker.
Other factor that increased risk
In accordance with the operator’s training, pilots routinely used increased angle of bank (45–60°) turns at low altitude to position the aircraft onto survey lines. This increased the risk of an aerodynamic stall at altitudes from which recovery may not be possible.
Protective clothing and helmets
At the time of the accident, the pilot was not wearing any protective clothing or a helmet. The use of such equipment was not required by the regulator, or the operator having considered environmental, comfort, and cockpit space aspects. Instead, it was left to the individual pilot’s discretion.
The ATSB’s aviation medical specialist indicated that protective clothing and helmets may reduce the magnitude of injuries in an accident. While they were unable to comment on the effectiveness of these items for this accident, it was acknowledged that these items would not have protected the pilot from smoke inhalation.
In some cases, occupants survive an accident only to succumb to hazards such as fire, drowning or environmental elements such as heat and cold (Shanahan, 2004). IAGSA recommended that survey pilots/crew wear protective clothing, not just as fire protection in the event of an accident but to also provide coverage from the elements while waiting for rescue or in a survival situation. Similarly, the Basic Aviation Risk Standard also recommended that all flight and aircrew wear protective clothing during operations. It is therefore important that these hazards have been considered to enable the best opportunity for survival in the event of an accident.
Other factor that increased risk
The operator did not require its pilots to wear protective clothing or helmets during low‑level survey operations, nor were they required to do so by regulations. However, the use of such has been recommended by industry to improve survivability in the event of an accident.
Risk management
In August 2019, MAGSPEC Aviation implemented a health, safety and environmental management system (HSEMS), which was intended tomeet theCivil Aviation Safety Authority (CASA) safety management system (SMS) requirements. It also provided more generalised guidance on the management of risk within the organisation. However, as an SMS was not required by regulation, it was not assessed by CASA. The ATSB acknowledges that an operator’s SMS, in this case HSEMS, will evolve and mature with time. Significant events like accidents provide an opportunity to assess if the system is operating in a way that assures the highest level of safety given the nature of their operations.
Acknowledging the CASR Part 138 requirements for aerial work operators to undertake risk assessments, which came into effect about 3 months prior to the accident, the ATSB reviewed the safety risk management component of the HSEMS. The HSEMS manual had detailed the 5‑stage process for risk management. However, there was no requirement in the operator’s manuals, as required by Part 138, to conduct a pre‑operational risk assessment nor had one been completed, as confirmed by the CP.
The absence of a pre‑operational risk assessment did not allow formal mitigation strategies, nor provide assurance that the risk level associated with low‑level survey operations was as low as reasonably practical. For example, the operator reported that the survey flights were often flown at about 30 m (100 ft) above ground level. While low operating heights were specified in the job safety analysis (JSA), there was no formalised risk controls referred to in the JSA. The accident survey flight had been flown at 25 m (85 ft) and this had been accepted on the basis of the reconnaissance flight, without any formal identification and implementation of supporting risk controls. While IAGSA acknowledged that stipulating a fixed minimum safe survey height was not practical given differences in survey conditions and aircraft characteristics, a pre‑operational risk assessment for operations at a reasonably anticipated operating height may have provided a foundation from which to adequately assess any variations to this height.
Further, the operator routinely flew consecutive survey lines, which used increased (steep) angle of bank procedure turns (45–60°) to manoeuvre between the lines. There was no assessment to identify any risks associated with conducting higher angle of bank turns at low-level to ensure that reasonable mitigations were implemented, and appropriate safety margins were applied.
The HSEMS further outlined that non‑site‑specific hazards were reported in their online SMS program, but due to the varying nature of operations, a separate site‑specific assessment of each survey job would be completed using the JSA. With the JSA, each survey task was assessed in isolation, with no reference to previous JSAs to ensure that applicable risk controls continued to be applied and/or were appropriate. Also, the JSA did not benefit from being informed by an overarching pre‑operational risk assessment. Therefore, as the predominant method for assessing operational risk, the JSA did not provide assurance that all hazards would be identified, and the associated risks would be assessed and mitigated.
As noted by the International Civil Aviation Organization (2018), safety risk management activities should be documented and the Part 138 Manual of Standards stipulated that the operator’s pre‑operational risk procedures were to include the use of a risk register. The CP reported that an operational risk register was not being maintained as part of their HSEMS at the time of the accident. While non‑site‑specific hazards would be recorded and assessed in the online SMS program, there was a missed opportunity to record the site‑specific hazards identified from the individual JSAs. Therefore, without a risk register, the operator’s ability to track, monitor, and mitigate all known hazards, and assess the effectiveness of existing risk controls was limited.
In interactions with CASA during the transition phase to Part 138 and the level 1 surveillance event post‑accident, there was no commentary related to the adequacy of the operator’s operational risk management processes. On that basis, the operator was of the understanding that the JSA met the risk assessment requirements of Part 138 inclusive of a pre‑operational risk assessment. However, CASA has since advised the ATSB that the JSA did not meet the requirements of a pre‑operational risk assessment.
Other factor that increased risk
MAGSPEC Aviation's safety risk management processes did not include a pre‑operational risk assessment that recognised the generic risks and hazards common across that type of operation nor was a risk register maintained. Consequently, there was limited assurance that all the risks had been identified and that all reasonable mitigations had been applied. (Safety issue)
Survey manoeuvres
As emphasised by IAGSA, conducting steep turns at low level can present challenges for fixed‑wing aircraft as any margin above the stall speed can quickly diminish and there may be limited height within which to respond to an unexpected situation. The ATSB’s analysis of the flight data showed there was some variation in the angle of bank used during the procedure turns on the accident flight, ranging from 43° up to the Cessna U206G angle of bank limit of 60°. At this limit, the stall speed increases by about 40%. The data also indicated that the procedure turns were conducted at an average of about 200 ft above ground level, which was lower than what was explained by the CP.
Similarly, a review of the morning pilot’s flight and discussions with other company pilots identified that there were differences in the individual turn techniques, demonstrating variations of the procedure turns.
While 45–60° angle of bank procedure turns were being taught, the operations manual did not include any policy or procedure for this manoeuvre. Further, there were no specific limits identified, such as a minimum turn height or maximum angle of bank, to establish appropriate safety margins such as that recommended by IAGSA.
ATSB research investigation report B2004/0337 discussed the importance of operational procedures:
The absence, deficiency or inappropriateness of operating procedures for operators may increase the risk to aviation safety.
The absence of standardised procedures means there may be considerable differences in the techniques used by different operators and contracting organisation staff to conduct tasks. Processes that are used to accomplish a particular task will evolve through a process of experience and passing on this information, often by word of mouth. There will be inconsistencies in how the task is accomplished, as different staff and operators will have differing levels of competence and experience, and different solutions to the same problem will have naturally evolved. The organisation that is managing the operation in such an uncontrolled environment will not be in full control or fully aware of how its tasks are being accomplished and therefore will have less control over the safety of the operation.
While the ATSB was unable to determine the circumstances that led to the loss of control, an operator’s expectations and desired safety margins should be documented to minimise variation and ensure operations are performed safely. Otherwise, without formal procedures, pilots are required to exercise judgement based on their experience, skills and knowledge.
Other factor that increased risk
The operator’s pilots were trained to, and routinely flew survey patterns utilising steep turns at low level. However, procedures or limitations specific to these manoeuvres were not included in the operations manual, which increased the risk of inconsistencies in the application of those manoeuvres and reducing the safety margins available.
Flight following
Survey flights are often conducted over remote, inhospitable terrain where regular communication services may not be available. Therefore, the use of satellite‑based flight following services are essential for providing real‑time monitoring of an aircraft’s location and for an efficient search and rescue response.
The operator had installed Spidertracks to all its aircraft and there was an expectation that an automatic alert would be received from the system in the event of emergency. However, there was no requirement and supporting procedure to check the functionality of the system prior to each flight. In this case, the alert function had not been activated for multiple flights, including the accident flight, which potentially influenced the delayed emergency response. Also, while the ground operator assigned to each tasking was responsible for providing flight following services, there was no expected schedule for checking the satellite tracking nor any procedure detailing the expectations of this role. Despite this, given the severity of the pilot’s injuries, it was very unlikely that a prompt emergency response would have changed the outcome.
It is important that an emergency response plan clearly identifies the notification and escalation triggers to avoid delays. Satellite tracking systems are useful in their ability to provide early notification of an emergency, especially in cases where the occupants have been incapacitated or otherwise unable to raise an alarm. However, their usefulness can only be realised if, when installed, they are correctly configured and operating as expected, otherwise increasing the risk of a delayed response.
Other factor that increased risk
While the operator’s aircraft were fitted with a satellite‑based flight following system, there was no requirement nor were there supporting procedures to confirm the set‑up and functionality of the system prior to flight or to monitor the system during flight. This increased the risk of the system not operating as expected and not providing early notification of an emergency.
Regulatory oversight activity
Since 2019, 3 ATSB investigations have been published identifying that regulatory oversight did not formally include the nature of the operator’s primary activities, the inherent threats or hazards associated with those activities, and the risk controls for managing those threats or hazards.
The ATSB acknowledges that CASA’s regulatory oversight activities were subject to normal constraints of time and resources, which may limit an ability to identify issues. Therefore, regulatory surveillance cannot examine every aspect of an operator’s activities, nor identify all the limitations associated with these activities.
The initial air operator’s certificate assessment of the operator and CP focused on the generic regulatory requirements and there were no criteria to evaluate their primary activity of low‑level survey operations. Although CASA had considered the operator and its key personnel as being suitable to conduct the proposed operations, there was no evidence that the processes and procedures for the primary activity had been specifically examined.Likewise, while the operator’s pilots held the appropriate low-level rating, there were no records to indicate that a detailed assessment of how the operator would address the risks associated with low flying had been conducted as part of the low flying approval.
Prior to this accident, the operator had undergone surveillance twice in 2018, following the first occurrence. Operational standards were included in the scope for both surveillance events but there were no related findings made by CASA nor was there any indication to what extent the operator’s low-level survey operations were examined.
The last AHPI review in early 2022 also noted that no post‑authorisation review (PAR) had been conducted following the initial issue of the air operator’s certificate (AOC) and there were no CASA records of action following the 2019 and 2020 occurrences. Consequently, it was recommended that a surveillance activity take place. The same recommendation was also made following this accident. The subsequent surveillance event in 2023 identified that the operator had limited documented operational procedures and training related to low‑level flight techniques.
CASA advised that a PAR (a type of level 1 surveillance) was likely to have been covered by an alternative level 2 surveillance event. The ATSB noted that a level 1 event was more comprehensive than a level 2, and for a PAR, was intended to ensure that the entry control requirements were being met following the initial issue of an AOC. As the CASA officers had made comments about a PAR having never been conducted, it was unclear whether the level 2 was sufficient to have been considered as having met the requirement of a PAR.
While none of CASA’s activities specifically focused on topics related to low‑level survey operations, for example survey patterns and heights, it was difficult to determine whether additional focus, through the conduct of a level 1 PAR for example, would have identified the specific aspects as found in the post‑accident surveillance event. However, CASA has since strengthened its AOC entry control procedures and surveillance planning and scoping to include more emphasis on assessing the primary activity including the use of a specific worksheet that highlights areas specific to Part 138 operators. Consideration of the primary activity provides a level of assurance that operators continue to meet the established requirements and function at the level of competency and safety required to undertake the activity for which they have been approved to perform.
In addition to the above, and as previously discussed, the ATSB identified deficiencies with the operator’s risk management processes. As the requirement for risk assessments only came into effect about 3 months prior to the accident, with the introduction of Part 138, there was limited opportunity for CASA to review these processes within that period. It was also noted that CASA had intended to look at the operator’s Part 138 compliance at the next scheduled surveillance event.
The 2023 surveillance event, which was also a review and follow-up to the accident, was a level 1 surveillance and included risk management within the scope of that activity. However, there were nil findings or observations identifying that there was no pre‑operational risk assessment and risk register, although required under Part 138. As an unintended consequence of this and the transition process to Part 138, the operator was of the understanding that the JSA satisfied this requirement. However, CASA has since indicated to the ATSB that the JSA did not meet the requirement of a pre‑operational risk assessment. While post‑accident, the 2023 surveillance event was a missed opportunity for CASA to identify the deficiencies in processes and inform the operator’s understanding of their risk assessment obligations under Part 138.
Other factor that increased risk
The Civil Aviation Safety Authority regulatory oversight of the operator had not specifically included the primary activity of low‑level survey flights, or the processes and procedures designed to reduce the risks associated with that activity.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision with terrain, involving a Cessna U206G registered VH-JVR, 124 km west of Norseman, Western Australia, on 3 March 2022.
Contributing factors
It was likely that, during a manoeuvre to intercept the next survey line, for undetermined reasons, control of the aircraft was lost at a height from which recovery was not possible, resulting in a collision with terrain.
Other factors that increased risk
An emergency response was not initiated until 30 minutes after the aircraft's estimated time of arrival, which was 3 hours after satellite tracking had stopped and attempts to contact the pilot had been unsuccessful. Although an earlier response was very unlikely to have altered the outcome in this case, minimising the time for search and rescue and enabling emergency services to respond as quickly as possible may increase the chances of a successful outcome.
In accordance with the operator’s training, pilots routinely used increased angle of bank (45–60°) turns at low altitude to position the aircraft onto survey lines. This increased the risk of an aerodynamic stall at altitudes from which recovery may not be possible.
The operator did not require its pilots to wear protective clothing or helmets during low‑level survey operations, nor were they required to do so by regulations. However, the use of such has been recommended by industry to improve survivability in the event of an accident.
MAGSPEC Aviation's safety risk management processes did not include a pre‑operational risk assessment that recognised the generic risks and hazards common across that type of operation nor was a risk register maintained. Consequently, there was limited assurance that all the risks had been identified and that all reasonable mitigations had been applied. (Safety issue)
The operator’s pilots were trained to, and routinely flew survey patterns utilising steep turns at low level. However, procedures or limitations specific to these manoeuvres were not included in the operations manual, which increased the risk of inconsistencies in the application of those manoeuvres and reducing the safety margins available.
While the operator’s aircraft were fitted with a satellite-based flight following system, there was no requirement nor were there supporting procedures to confirm the set‑up and functionality of the system prior to flight or to monitor the system during flight. This increased the risk the system not operating as expected and not providing early notification of an emergency.
The Civil Aviation Safety Authority regulatory oversight of the operator had not specifically included the primary activity of low-level survey flights, or the processes and procedures designed to reduce the risks associated with that activity.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: MAGSPEC Aviation's safety risk management processes did not include a pre‑operational risk assessment that recognised the generic risks and hazards common across that type of operation nor was a risk register maintained. Consequently, there was limited assurance that all the risks had been identified and that all reasonable mitigations had been applied.
Safety recommendation to MAGSPEC Aviation Pty Ltd
The ATSB makes a formal safety recommendation, either during or at the end of an investigation, based on the level of risk associated with a safety issue and the extent of corrective action already undertaken. Rather than being prescriptive about the form of corrective action to be taken, the recommendation focuses on the safety issue of concern. It is a matter for the responsible organisation to assess the costs and benefits of any particular method of addressing a safety issue.
Safety recommendation description: The Australian Transport Safety Bureau recommends that MAGSPEC Aviation Pty Ltd develops and maintains a pre-operational risk assessment and risk register that is separate to its existing job safety analysis process. This should encompass the generic risks and hazards common across its operations and allow it to fully consider operational risks beyond individual survey tasks.
Safety action not associated with an identified safety issue
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Additional safety action by MAGSPEC Aviation Pty Ltd
In response to this accident, MAGSPEC Aviation has taken the following safety action:
The JSA has been revised to include the selection of consequence and likelihood to determine a risk for each identified hazard. It also recorded mitigations that would be applied. The operator advised the overall and highest risk scores determined whether the survey could proceed and/or if it was likely to increase the fatigue and safety of the operation to unacceptable levels.
The health, safety and environmental management system has been incorporated into the operations manual as an appendix.
The emergency response plan was revised to clarify initiation triggers and accounted for a satellite tracking system failure. The operator has also equipped its operations room with 2 dedicated monitors for the sole purpose of tracking aircraft.
The operations manual now includes a minimum speed versus angle of bank section and pilot actions if an aircraft cannot achieve or maintain the required speed.
Guidance on procedural turns has been formalised in the operations manual. Although there is a description of how to conduct the turn, the manual also explains that this was the desired turn method and may not always be possible (due to terrain, obstacles, block shape et cetera).
The operations manual has been amended to clearly state that an aircraft was required to have a fixed emergency locator transmitter. If this becomes unserviceable or has to be removed, the aircraft can only be flown for the purpose of having the issue rectified.
Each pilot has been issued with a personal locator beacon, individually registered with the Australian Maritime Safety Authority. Pilots are required to keep the device on their person while operating company aircraft. The operations manual also states that the personal locator beacon cannot be carried/used if not tested.
Follow-up with Spidertracks is to be made on each occurrence of dropout, service interruption or delay in tracking updates and numerous improvements made to the interface. The operator advised that the SOS automatic watch function and alert has been investigated and rectified. A checklist item has been added to ensure Spidertracks is correctly functioning prior to departure.
They no longer operate at survey heights below 30 m.
The operator identified that its low‑level training syllabus was lacking parameters to mark a pilot as competent, especially in critical phases of flight. This has been formalised to match what had been done practically.
Its operations manual is currently under review by CASA. This includes items to enable Flight Safety Foundation’s Basic Aviation Risk Standard accreditation. Just prior to final publication of this report, the operator advised that it had been awarded the Basic Aviation Risk Standard accreditation.
Glossary
AGL
Above ground level
AHPI
Authorisation holder performance indicator
AoA
Angle of attack
AOC
Air operator’s certificate
CAR
Civil Aviation Act
CASA
Civil Aviation Safety Authority
CASR
Civil Aviation Safety Regulations
CoG
Centre of gravity
CP
Chief pilot
ETA
Estimated time of arrival
ELT
Emergency locator transmitter
G
Gravity
GPS
Global positioning system
HSEMS
Health, safety and environmental management system
IAGSA
International Airborne Geophysics Safety Association
JRCC
Joint Rescue Coordination Centre
JSA
Job safety analysis
MOS
Manual of Standards
PLB
Personal locator beacon
POH
Pilot’s operating handbook
SMS
Safety management system
Sources and submissions
Sources of information
The sources of information during the investigation included:
MAGSPEC Aviation Pty Ltd
other pilots who conducted flights for the operator
recorded data from the satellite tracking device
the maintenance organisation
aviation medical specialist
Pathwest Laboratory Medicine WA
Civil Aviation Safety Authority
Bureau of Meteorology
Western Australia Police Force
Australian Maritime Safety Authority Joint Rescue Coordination Centre
Spidertracks Ltd.
References
Australian Transport Safety Bureau. (2005). Aviation Research Investigation Report B2004/0337 Risks associated with aerial campaign management: Lessons from a case study of aerial locust control. Retrieved from /publications/2005/aerial_locust_control/
Australian Transport Safety Bureau. (2013). ATSB Research Investigation AR-2012-128 A review of effectiveness of emergency locator transmitters in aviation accidents. Retrieved from /publications/2012/ar-2012-128
International Airborne Geophysics Safety Association. (2017). Safety Policy Manual (v2017-1201). Retrieved from https://iagsa.ca/
International Civil Aviation Organization. (2018). Safety Management Manual, fourth edition, Montréal: International Civil Aviation Organization.
Shanahan, D.F. (2004). Human tolerance and crash survivability. RTO HFM Lecture Series on ‘Pathological Aspects and Associated Biodynamics in Aircraft Accident Investigation’. Madrid, Spain.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
MAGSPEC Aviation Pty Ltd
other pilots who conducted flights for the operator
Civil Aviation Safety Authority.
Submissions were received from:
MAGSPEC Aviation Pty Ltd
Civil Aviation Safety Authority.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau.
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1]Aerodynamic stall: occurs when airflow separates from the wing’s upper surface and becomes turbulent. A stall occurs at high angles of attack, typically 16˚ to 18˚, and results in reduced lift.
[2]Integral fuel tanks are part of the aircraft structure. They are manufactured by assembling parts of the aircraft structure with sealant to form a fuel-tight compartment, most commonly in the wings.
[3]A supplemental type certificate is a type certificate issued when an applicant has received regulatory approval to modify an aeronautical product from its original design. The supplemental type certificate, which incorporates by reference the related type certificate, approves not only the modification but also how that modification affects the original design.
[4]The system was pre-programmed by the ground operator prior to departure, minimising any manipulation required by the pilot during flight.
[5]From the pilot’s operating handbook, the calibrated airspeed and indicated airspeed in the range of interest were within 1 kt, so for the purposes of the analysis were considered equivalent. The term indicated airspeed is used throughout the analysis.
[6]G load: the nominal value for acceleration. In flight, G load represents the combined effects of flight manoeuvring loads and turbulence and can have a positive or negative value.
[7]A steep turn is one greater than a 45° bank angle.
[8]Carbon monoxide is a colourless, odourless, tasteless, and poisonous gas that is produced as a by-product of burnt fuel. Exposure to a leak from the exhaust of an aircraft engine into the cabin can lead to elevated levels of carbon monoxide, which can impair cognitive function.
[10]CAR 157 (2) requires that an aircraft shall not fly over a populous area at a lower height than 1,500 ft or any other area at a lower height than 500 ft. CAR 157 (4)(b) states that the provisions of CAR 157 (2) shall not apply if the aircraft is engaged in aerial work operations and the operator has a permit from the authority (CASA) to do so.
[11]As the wing to which the stall warning vane is mounted approaches the critical AoA, the relative air flow changes direction and will push the vane up, closing a switch in the device. This will activate a warning horn.
[12] Donesafe is a web and application‑based safety management system tool.
[13]This timeframe has since changed with the most recent being 12-18 monthsfollowing the initial issue, depending on the type of authorisation issued (CASA Surveillance Manual version 5.2 ‑ May 2024).
Preliminary report
Report release date: 26/05/2022
This preliminary report details factual information established in the investigation’s early evidence collection phase, and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On 3 March 2022, a Cessna U206G, registered VH-JVR, was being operated by MAGSPEC Aviation for low-level, geophysical survey flights to the west of Norseman, Western Australia.
At about 1200 WST,[1]the aircraft departed Kalgoorlie, Western Australia, for the survey block about 120 km west of Norseman. The pilot was the sole occupant on board the aircraft.
Weather conditions in the survey area were fine with light southerly winds. Earlier in the morning, another company pilot had flown the aircraft on a survey flight. That pilot had conducted a confirmatory reconnaissance flight, noting no major obstacles or issues other than a few taller trees. This information was passed to the pilot of the accident flight before they departed.
The survey lines were parallel to each other at 25 m spacing in an east-west orientation. The survey lines were to be flown at a height of 25 m (82 ft) above ground level (AGL).
The pilot commenced the first survey line at about 1252. At 1343, the GPS tracking device recorded the aircraft was on a westerly heading at a speed of 116 kt and a height of 1,398 ft (GPS height).[2] This was the last position recorded and the height was consistent with the intended survey height above ground level.
The aircraft did not return to Kalgoorlie by the pilot’s nominated estimated time of arrival of 1630, and the operator commenced its emergency response. The operator had another aircraft and pilot at Norseman, which was dispatched to VH-JVR’s last known position; however, that pilot was not able to locate the aircraft.
The Joint Rescue Coordination Centre (JRCC) initiated a search operation after it was advised by the operator at 1700 that the aircraft was overdue. A search aircraft located the aircraft wreckage at 1852, approximately 3.2 km west of its last recorded position (Figure 1). That aircraft’s crew were not able to establish communications with the pilot of the accident flight. The JRCC also deployed a rescue helicopter to the site, and its crew confirmed that the pilot had been fatally injured.
Figure 1: VH-JVR's accident site and last recorded position
The first survey line was flown in a westerly direction. The direction of flight was reversed on each subsequent line.
Source: Recorded flight path data and Google Earth, annotated by the ATSB
Context
Pilot information
The pilot held a valid commercial pilot licence (aeroplane) with a multi-engine command instrument and low-level ratings. Their last flight review was completed in June 2021 and their class 1 medical was valid until June 2022. The pilot had held a low-level rating since June 2021 and had completed the operator’s low-level survey training in July 2021.
The pilot had previously worked as a flight instructor and high-level survey pilot. At the time of the accident, the pilot had about 1,772 hours total, of which about 557 hours was with the operator.
Aircraft information
General
VH-JVR was a Cessna U206G Stationair, which was a single-engine, fixed landing gear aeroplane powered by a Continental IO-520-F piston engine (Figure 2). It was manufactured in 1978 with serial number U20604795 and was first registered in Australia in 1998. Its last periodic inspection was in March 2022 and it had accrued almost 8,000 hours total time in service.
Modifications
VH-JVR had been modified to conduct geophysical survey flights. A magnetometer boom was installed at the rear of the aircraft and associated survey equipment was in the rear cabin. The survey equipment had its own separate power supply. The aircraft also had a GPS tracking device.
The aircraft had also been modified with a fuel selector valve from a C210, which enabled the selection of both fuels tanks to supply the engine at same time.
Figure 2: VH-JVR
Source: Jarrod Swanwick (via www.jetphotos.com), modified by the ATSB
Site information
The aircraft was located in dense bushland 124 km west of Norseman. Access to the site was difficult with the nearest vehicle-accessible track only reaching to within 4 km of the accident site. An additional track was cleared through bushland to enable vehicle access to the accident site.
Damage at the point of impact indicated that the aircraft initially struck trees in an upright but relatively steep nose-down attitude. The impact caused the left wingtip and aileron to separate from the aircraft. The aircraft then impacted the ground on its left side and continued through the bush in a southerly direction, coming to rest about 45 m from the initial point of impact (Figure 3).
The aircraft felled a number of trees and several parts had separated from the main body, including the nose gear assembly, left main gear, left door, windscreen and sections of the lower engine cowling and lower engine components (Figure 4). There was no indication of fire in the wreckage trail, either in the bushland or aircraft components. However, the remainder of the aircraft was almost entirely destroyed by a post-impact fire. The propeller had separated from the engine and was located towards the rear of the wreckage and the engine had been detached from its mounts. The right wing was relatively intact as was the magnetometer boom, albeit damaged by fire (Figure 5).
Figure 3: Wreckage trail looking south towards the main wreckage
Source: ATSB
Figure 4: Wreckage trail looking north towards the impact area
Source: ATSB
Figure 5: Main wreckage
Source: ATSB
Wreckage examination
The wreckage was examined on-site and to the extent possible (given the post-impact fire). The following observations were made:
all components of the aircraft were accounted for at the site
there were no indications of pre-impact structural failures
flight control continuity was established
propeller damage and propeller strike marks observed in the trees were indicative of the engine producing power at the time of impact
there were no indications of pre-impact damage or defects to the engine
the flaps were fully retracted (although only the right wing was able to be examined due to fire damage)
there was no indication of a pre-impact, inflight fire (although the extent that this was able to be verified was limited due to the post-impact fire).
Further investigation
To date, the ATSB has:
examined the wreckage
recovered aircraft components and other items for further analysis
interviewed relevant parties
collected aircraft and operator documentation
collected the pilot’s records.
The investigation is continuing and will include:
further review of aircraft and operator documentation
further review of the pilot’s records
further review and examination of aircraft components and other items recovered from the accident site
further analysis of flight path information from the aircraft’s GPS tracking device
review of the risk controls in place for low-level survey work.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Acknowledgements
The ATSB would like to acknowledge the significant assistance provided by the Western Australia Police Force and Poseidon Nickel Ltd during the onsite investigation phase.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 11 March 2022, at about 1050 local time, the pilot of a Bell Helicopter Company B206L-1, registered VH‑BHF and operated by Heli Surveys Pty Ltd, departed Jindabyne aerodrome, New South Wales, to conduct a weed survey task on behalf of the New South Wales National Parks and Wildlife Service (NPWS). On board were the pilot and 4 NPWS officers. At about 1112, at a low level and low speed over the Snowy River, control of the helicopter was lost. While attempting an emergency landing in the river, the helicopter collided with a large boulder. Three of the occupants received serious injuries and 2 received minor injuries. The helicopter was destroyed.
What the ATSB found
The ATSB found that, to conduct the weed survey above the riverbank, the helicopter was flown at low-level, at a slow speed, and yawed to the right by about 45°. It was also noted that the helicopter was operating at a high gross weight and higher density altitude. In combination, these conditions were conducive to the onset of a loss of tail rotor effectiveness. As such, it was likely that a loss of tail rotor effectiveness occurred at an insufficient height to recover and avoid a collision with terrain. Following the collision into the river, the carriage of dedicated emergency locator transmitting devices allowed for a timely response for retrieving the occupants.
Further, one of those on board was not required for the survey task, which unnecessarily exposed them to the risks associated with low-level flight. While the client’s operating procedures referred to ‘essential personnel’, they did not provide a definition or specify the roles and responsibilities of these personnel.
The ATSB also identified that the operator’s risk assessment for low-level operations did not contain the hazard and control measures to avoid the likelihood of loss of tail rotor effectiveness. Further, there was no requirement for its pilots to conduct pre-flight risk reviews to ensure that operations could be conducted without unacceptable safety risk.
What has been done as a result
Heli Surveys conducted a review of its risk management processes and made changes to its operational conduct. Its changes focused on identifying flight‑related hazards that included loss of tail rotor effectiveness and compiling mitigation controls in a dedicated risk assessment. Other changes included the introduction of a ‘Hazardous Flight Conditions’ course for pilots and a requirement for flight crews to ensure that only essential crew were to be on board its helicopters.
The NPWS revised its aviation safety policy and developed an aviation safety management system to enhance safety and manage risk across its aviation activities and operations. To define essential personnel, the NPWS committed to developing detailed task profiles to ensure that the roles and responsibilities of all personnel were clearly defined and committed to the development of task‑specific risk profiles to manage risks associated with its aerial work activities.
Safety message
Survey flights, particularly when performed in alpine environments, are generally conducted at low level and slow speeds. This creates a high-risk operating environment that requires effective risk management. Risk management should include an overarching pre‑operational risk assessment to identify the hazards and risks common to that type of operation. This assessment can then be used to inform the management of risk for specific taskings including a pilot’s pre-flight risk review, to ensure the operation can be conducted safely.
This accident further highlighted the benefits of carrying multiple position transmitting devices. This not only eliminates potential doubt associated with transmissions generated from inadvertent beacon activation but can accelerate an emergency response.
The occurrence
On 11 March 2022, at about 1050 local time, the pilot of a Bell Helicopter Company B206L-1 helicopter, registered VH‑BHF and operated by Heli Surveys Pty Ltd, departed Jindabyne aerodrome, New South Wales, to conduct a low-level English Broom weed[1] survey task on behalf of the New South Wales National Parks and Wildlife Service (NPWS) (Figure 1). On board were the pilot and 4 NPWS officers.[2]
Following departure, the flight tracked north along the western side of Lake Jindabyne and at about 1055, the pilot turned north-west and tracked upstream along the Snowy River before turning south-west towards Island Bend. At about 1102, the helicopter passed overhead Island Bend where a clump of the weed was located. This local infestation provided an opportunity for the NPWS officers to familiarise themselves with spotting the target weed in the local environment, to assist with identification during the survey.
From Island Bend, the flight continued south-west, following the course of the river. At 1110:35, the helicopter approached Guthega (Munyang) hydro‑electric power station where the pilot commenced a left turn, to pass to the east of the power station.
Figure 1: VH-BHF flight path from Jindabyne aerodrome to Guthega power station with inset showing location relative to capital cities
Source: Google Earth and TracPlus data, annotated by the ATSB
At 1110:47, and now south of the power station, the pilot commenced a right, high orbit to remain clear of power lines in the area and return towards the river course.
By 1111:17, the helicopter was heading downstream above the southern riverbank and established in a descent towards the river in preparation for commencing the weed survey (Figure 2).
Corroborating reports from the occupants of the helicopter, which included the pilot, indicated that due to the seating position of the NPWS officers (3 seated on the left side of the helicopter), the later part of the descent was conducted with the nose of the helicopter yawed to the right about 45°. The right yaw was in response to the officers’ request to provide the best view of the riverbanks for them to identify and map the locations of the English Broom weed. The officers reported that they asked the pilot to fly lower and sideways to enhance their view. The pilot reported to the ATSB that, prior to setting up the right yaw position, the helicopter’s speed was about 30 kt and they noted they had sufficient power with no abnormal engine indications.
As the helicopter descended past Pipers Creek, the pilot reported that their vision of trees and other obstacles was obscured by the helicopter’s instrument console. To improve their vision for the final descent to the river, the pilot indicated that they ‘touched’ the left anti-torque pedal[3] to straighten the helicopter ‘a bit’, upon which the helicopter started an uncommanded yaw[4] to the right.
In interview with the ATSB, the pilot stated that they believed they had full and free movement of the anti-torque pedals until the uncommanded yaw to the right started. After the yaw started, they felt that the helicopter did not respond to their pedal inputs, but they could not recall exactly what inputs they made. The pilot did not recollect any shock loading of the tail rotor, such as from a bird or tree strike. The officers reported that, when the uncommanded right yaw started, they thought it was a pilot‑initiated turn and that they were clear of trees and there were no physical knocks or signs of a failure before the yaw commenced.
After the first turn, when the helicopter was facing downstream, the pilot attempted to gain forward speed, but the helicopter continued to yaw right, and the yaw rate started to accelerate. At 1111:58, when about 200 m past Pipers Creek, the pilot reported realising their only landing option was in the river and, to do so, they rolled the throttle to idle, which stopped the yawing motion. The helicopter entered an autorotation[5] with the pilot aiming for a spot in the river. The pilot attempted to cushion the landing but did not see a large boulder in the water at their aim point.
At 1112:04, the helicopter collided with terrain. Three occupants received serious injuries, and 2 sustained minor injuries. The helicopter was destroyed.
Figure 2: Approach to Guthega power station, orbit to the south, descent and collision with terrain
Source: Google Earth and TracPlus data, annotated by the ATSB
At the time of the accident, the operator had another helicopter in the local area conducting sling‑work operations. At around 1130, the pilot of that helicopter, who was also the head of flying operations, received a report[6] of an alert notification from the emergency locator transmitter on VH‑BHF, and a subsequent report of a personal locator beacon activation. Aided by their onboard resources, the pilot identified the last recorded position of VH-BHF that was transmitted by its satellite‑based tracking system (TracPlus) and immediately ceased the sling-work operation and departed for that recorded position. While enroute, the pilot notified emergency services and directed their ground‑based resources in the local area to the expected helicopter location.
The pilot located VH-BHF at about 1138 and confirmed the accurate position with emergency services. While surveying the scene from overhead, they were joined by another of the operator’s helicopters, and that pilot was able to unload an air crew person at the accident site. The air crew person was equipped with a first aid kit and provided a communications link between the ground and the overhead helicopters. At about 1210, the operator’s ground-based staff arrived to provide assistance and reported that emergency services had started to arrive. Following initial treatment, 3 of the injured persons were airlifted to hospital while the remaining 2 were able to walk from the site to awaiting ambulances.
Context
Personnel information
Pilot
Qualifications and experience
The pilot held a valid class 1 aviation medical certificate and a Commercial Pilot’s Licence (Helicopter) with single‑engine helicopter and low‑level rating, and a gas turbine endorsement. The operator’s pilot record sheet, dated 2 November 2021, indicated the pilot had accrued 900 hours turbine experience from a total of 2,065 flying hours experience. The pilot had also logged 530 hours aerial work and low flying, and 20 hours mountain flying. In the 28 days prior to the accident, the pilot had accrued 47.1 hours flight time, and 98.7 hours in the previous 90 days. In total, the pilot had 145 hours experience on the Bell 206L-1 helicopter, which included 9.3 hours in the previous 90 days.
Operator training
The pilot joined the operator, Heli Surveys, in early November 2021. On 21, 22 and 23 October 2021 they completed 6 pre-employment check flights on the AS350 helicopter with a contracted training and checking organisation. The syllabus for the checks included low flying within the normal procedures and tail rotor malfunction, autorotation, fire, jammed controls and system failures within the emergency procedures.
The pilot reported that a loss of tail rotor effectiveness (LTE) (refer to section titled Loss of tail rotor effectiveness) would have been covered in their training history at some stage but could not recall any specific occasion, and that they had never experienced it before in flight. The operator’s head of flying operations (HOFO) reported that they conducted a flight with the pilot before they were released to line and was impressed with their attention and focus on control of the helicopter during take-off and landing. The HOFO did not specifically discuss LTE during their flight with the pilot but did discuss mountain and survey operations. They further reported that they considered LTE a component of the low-level flying conducted in the pilot’s pre‑employment check flights.
National Parks and Wildlife Service officers
The National Parks and Wildlife Service (NPWS) team on board consisted of:
A task coordinator who had the lead role in terms of liaising with the pilot and the other officers and was logging the location of the English Broom weed on a hand-held electronic device.
Two officers designated as primary observers (spotters). Their role was to look for the weed, and when a plant was identified, advise the coordinator. One of these observers was logging the position of the weed on a hand-held electronic device.
Another NPWS officer had joined the group given their employment as the area ranger. The survey task had provided the opportunity for the officer to familiarise themselves with the area from the air and observe the conduct of the weed survey task. While the officer did not have a specific function to perform for the survey, they assisted the team in locating the English Broom weed.
Helicopter information
General
VH-BHF was a Bell Helicopter Company B206L-1 powered by a Rolls-Royce model 250‑C30P gas turbine engine driving a 2‑blade main and tail rotor system. It was manufactured in the United States in 1979 and assigned serial number 45164. The helicopter was issued with an Australian Certificate of Airworthiness on 7 April 1987 and first registered in Australia on the same date. Including the pilot, the helicopter provided seating for 7 occupants. At the time of the accident, the helicopter had accumulated about 11,849 hours, total time in service.
Recent maintenance history
At the last 100-hour periodic inspection on 27 November 2021, a maintenance release was issued, permitting night visual flight rules[7] operations. The maintenance release showed that an engine hot start defect had been recorded in December 2021. Rectifications for that included the replacement of the engine turbine assembly, and post‑repair power assurance checks that were certified as completed on 14 February 2022, deeming the engine serviceable. The maintenance release also showed that:
other than items that would be addressed during a daily inspection, no maintenance was due
there were no defects that required rectification before the next flight
the helicopter had been flown for about 22 hours from when the maintenance release was issued prior to the accident.
Modifications
The helicopter was fitted with Van Horn Aviation 2062200-101/-301 tail rotor blades with a United States Federal Aviation Administration (FAA) approved rotorcraft flight manual supplement (206L1‑FMS‑901). The supplement stated that the tail rotor blade design increased the stall margin, thereby improving high altitude performance:
Satisfactory stability and control has been demonstrated in relative winds of 30 MPH (26 knots) sideward and rearward at all loading conditions…
The helicopter was also fitted with main rotor yoke part number 206-011-149-101 allowing flight operations up to a gross weight limit of 1,882 kg (4,150 lb), up from 1,837 kg (4,050 lb) as stated on the type certificate data sheet.
Weight and balance
The ATSB completed weight and balance calculations for the helicopter, considering the pilot and 4 NPWS officers on board. Including fuel, baggage and cargo, the helicopter all‑up weight at take‑off was determined to be about 1,842 kg, 40 kg below its gross weight limit of 1,882 kg, and within its centre of gravity limits. Accounting for fuel burn-off, the helicopter’s all-up weight at the time of the accident was about 1,799 kg, 83 kg below its gross weight limit.
Meteorological information
The Bureau of Meteorology grid point wind and temperature forecast (relevant to the accident) for 1100 on 11 March 2022 was 5 kt of wind from the west (280°) and a temperature of 8°C at 5,000 ft. The graphical area forecast, valid from 1000, was for visibility greater than 10 km with scattered[8] stratus cloud between 2,000 ft and 3,500 ft until 1100.
The nearest aerodrome with an automatic weather information service was Cooma, New South Wales, located 50 km east of the accident site at an elevation of 3,106 ft. The recorded conditions at Cooma at 1100 were a wind of 9 kt from 030°, visibility greater than 10 km, no cloud detected, a temperature of 13°C and QNH[9] at 1021.
The pilot reported fine weather conditions with light winds from the south-west of no more than 5 kt when in the vicinity of the power station, dropping to nearly nil wind conditions once below treetop height on descent towards the river. The NPWS officers reported that the weather was calm. One of the first responders provided a similar report of light and variable winds, as they noted that the wind conditions allowed each rescue helicopter to assume a different heading while hovering as the injured persons were winched on board.
A similar report regarding local weather conditions was received from the operator who maintained an airborne presence during the initial discovery of the wreckage and throughout the rescue operation. They described the conditions on the day as very good with visibility greater than 10 km and wind speed predominantly below 5 kt. They added that there was a very light wind flowing in the downstream direction of the river at the accident site.
Recorded data
A TracPlus™ RockAIR tracking device was recovered from the helicopter following the accident. The device recorded global positioning system tracking information at a frequency of 1 Hz on a removable micro-SD card. ATSB analysis of the recorded data for the last 60 seconds of the flight is shown in Figure 3 for illustrative purposes.
For a period of about 32 seconds before the helicopter started to yaw, the recorded data indicated that its groundspeed was below 25 kt and further decreased below 20 kt about 5 seconds before the yaw began. About 3 seconds after the yaw commenced, and from a height of about 200 ft above ground level, the helicopter’s rate of descent (vertical speed) increased and reached a peak of about 2,500 ft/min, consistent with the pilot rolling off the throttle and entering an autorotational descent. The data indicated that the yaw lasted for about 5 seconds and was arrested within about 3 seconds of the start of the descent. When the yaw stopped, the helicopter’s height was about 65–100 ft above ground level.
Figure 3: Ground positioning system flight tracking data over the last 60 seconds of recording
Graphical representation of flight data showing helicopter forward and vertical speeds, altitude, height above terrain and helicopter track with descriptive comments added. Source: TracPlus data, accessed and annotated by the ATSB
Wreckage and impact information
The accident site was located less than 600 m downstream from the Guthega power station (Figure 2) and 20 km north-west of Jindabyne, New South Wales. The helicopter landed on top of a large boulder in the shallows of the Snowy River and came to rest on a heading of 310°, with the fuselage canted significantly to the right (Figure 4).
The helicopter struck the boulder at a point forward of the external cargo hook fuselage mount and slightly aft of the forward skid gear cross tube. The impact with the boulder structurally damaged the helicopter, breaking the forward cockpit section from the cabin area, and resulted in the tailboom partially fracturing near its fuselage attachment point.
The tailboom fracturing and subsequent deflection likely resulted in a tail rotor ground strike and loss of a portion of a tail rotor blade, which was not recovered from the site. Apart from the missing section of tail rotor blade, the rest of the helicopter was present at the accident site. No evidence of a bird or in-flight tail rotor strike was identified and there was no post‑impact fire.
The location of the helicopter in the riverbed and the surrounding environment precluded a complete examination of the wreckage at the accident site. The operator reported receiving advice that anticipated water inflows at Guthega Dam would result in increased water levels downstream of the dam from water exiting the uncontrolled spillway. In response, the wreckage was removed from the accident site at the earliest opportunity, airlifted from the riverbed and relocated to a secure site in Cooma for detailed examination.
Figure 4: VH-BHF following collision with terrain against large boulder in the Snowy River, New South Wales
Source: ATSB
The ATSB’s site examination did not reveal any pre-existing defects that may have affected the operation of the helicopter or its systems. The detailed examination of the flight control systems in Cooma did not identify any pre-existing defects that may have affected the control of the helicopter.
Where evidence of structural fractures and breaks were identified, the failures were found to be fresh and were attributed to being either collision‑related, or as the result of torsional overload forces. Of note was the torsional overload of the tail rotor driveshaft at the tail rotor gear box location. This indicated that the driveshaft was driving the tail rotor when the tail rotor experienced a sudden stoppage (Figure 5).
The engine presented as intact, securely mounted, and with controls functional but with restricted movement due to fuselage damage. The compressor and turbine were found to spin freely. No defects were identified with the supply, delivery and quality of the fuel that was available to the engine.
The seating configuration of the helicopter consisted of 2 cockpit seats and, in the cabin section, a centre row of 2 aft-facing seats and a rear row of 3 forward‑facing seats. For the accident flight, the pilot was in the front right seat with an NPWS officer (coordinator/recorder) in the front left seat, another officer (area ranger – observer) in the centre row left seat (facing rearwards), and the 2 remaining officers in the left (observer/recorder) and right (observer) seats of the rear row (Figure 6). Each seat was equipped with a 4-point restraint harness.
Figure 6: VH-BHF cockpit and cabin seating layout and NPWS officers’ functional positions
Bell 206 LongRanger III seating layout adopted for illustrative purposes only. Source: FlyFlapper.com annotated by the ATSB
Injuries
The pilot, task coordinator, and observer in the rear‑facing cabin seat sustained serious injuries. The 2 observers in the rear row received minor injuries.
Evacuation
While airborne above the accident site, the HOFO reported they contacted the power station and advised them of the accident downstream of their location and for consideration of the possible impact on power generation commitments. They were advised that power generation would be postponed, however, water levels downstream of Guthega Dam were dependent on natural inflows and outflows from the dam.
At interview, 2 of the NPWS officers advised that they were aware that the water level would likely rise in response to power generation activity. As a precaution, after assisting the injured with evacuating from the helicopter, they were immediately moved to higher ground.
Survival equipment
The NPWS aviation standard operating procedure for low-level flying specified that, when engaged in such activities, helicopters were to carry an emergency locator transmitter (ELT) and be fitted with a tracking system that could be tracked by the agency. As such, the helicopter was equipped with an ELT, and a survival pack that included a personal locator beacon (PLB), a first aid kit and a satellite phone. A TracPlus RockAIR device was also mounted on the instrument console, which provided real-time location tracking of the helicopter through GPS technology. The tracking device was designed to transmit an alert if a sudden impact of 16g or more for a period greater than 10 milliseconds was detected.
ELT and PLB emergency radio beacons are used to provide a location fix on a person, aircraft or other vehicle (ATSB, 2013). ELTs are usually fixed in an aircraft and are designed to activate automatically during an impact, typically by a g-force[10] activated switch but can also be wired to be manually activated by a cockpit-located switch usually mounted within reach of the pilot or a front‑seat passenger. PLBs are designed for personal use and may be carried on the person or carried as part of a survival kit. They are manually activated and may be used as an alternative to a fixed ELT, provided certain requirements are met.
In the event of an accident followed by beacon activation, the aircraft wreckage and its occupants can be located quickly by search and rescue authorities. Finding the aircraft wreckage quickly not only increases the chance of survival of the occupants but also reduces the risk to pilots of search and rescue aircraft who commonly need to operate in marginal weather conditions and over mountainous terrain (ATSB, 2013).
The collision resulted in both the ELT and tracking device activating. The collision alerts were received by the operator (HOFO) and were followed by a third report of a PLB that was manually activated by one of the NPWS officers. This allowed the HOFO to promptly identify the last known position of VH-BHF and commence an emergency response. The operator reported that the multiple transmissions from independent sources provided the surety that a distress situation existed.
Operational information
Helicopter performance
The out-of-ground effect performance chart in the B206L-1 rotorcraft flight manual indicated the helicopter had the performance required to hover out-of-ground effect at the elevation and temperature conditions for the accident. The accident site was located at an altitude of 4,308 ft. Accounting for temperature and QNH, the density altitude for the flight just prior to the accident was calculated to be about 4,500 ft.
The recorded data for the flight indicated that the groundspeed had dropped below 20 kt before the loss of control, and accounting for density altitude influence, this equated to a calibrated[11] airspeed of about 1–2 kt below the groundspeed in nil wind. The height and airspeed of the helicopter at this time placed it inside the avoid area of the height-velocity diagram[12] (Figure 7 – left). The helicopter’s weight and density altitude also placed the operation outside of the weight-altitude limit for the height-velocity diagram (Figure 7 – right).
Consequently, the helicopter was operating in a region of the flight envelope where there was no assurance that a safe autorotation could be made without damage and injuries to occupants. At interview, the operator advised that flight operations in the avoid area was common practice, and necessary to effectively and accurately conduct a weed survey task.
Figure 7: B206L-1 flight manual performance charts showing operational caution zones and VH-BHF relative position in preparation for survey task
Source: Bell Helicopter Company, annotated by the ATSB
Aerial work operations
Heli Surveys
Heli Surveys Pty Ltd was approved by the Civil Aviation Safety Authority (CASA) to conduct various flight operations including Civil Aviation Safety Regulation (CASR) Part 138 aerial work operations. Its aerial work operations were varied and included roles associated with feral animal control and survey flights of pest animals, weeds and power lines.
Part 138 aerial work operations
CASR Part 138 and the Part 138 (Aerial Work Operations) Manual of Standards (MOS) addressed the certification, operational and safety risk management requirements for operators engaged in aerial work operations (CASA, 2021e). At the time of the accident, aerial work encompassed the core activities of external load operations, dispensing operations or task specialist operations.[13] Advisory circular AC 138-01 v1.0 Part 138 core concepts defined task specialist operations as:
carrying out a specialised activity using an aircraft in flight and includes training for such an activity. An example of a task specialist operation is a low level weed survey or pipeline inspection.
Additional guidance for aerial work operations applicable at the time of the accident was provided in advisory circular AC 138-05 v1.1 Aerial work risk management (July 2021b) and the Part 138 Acceptable means of compliance and guidance material – Aerial work operations v2.2 (December 2021f).
Conducting the survey flight
At interview, the HOFO described the accident task as an ad hoc type survey in which the helicopter would be flown up-valley and then down-valley to view both sides of the river and that the airspeed, direction and height was not prescribed. The HOFO expressed the view that the optimum profile for survey flights was a height of 300 ft and airspeed of 55 kt. However, if adopting that profile, it would make it impractical to identify English Broom weed in surveys of the Snowy River.
The HOFO reported that, from experience, they did not consider that it was unusual when the client presented with 4 NPWS officers for the conduct of the survey flight. In terms of managing client requests, all pilots are provided with a ‘stop work authority’ and can therefore decline a client request if they perceive a safety of flight issue.
The NPWS officers indicated that, on the morning of the accident flight, they discussed their English Broom weed survey plan while waiting for the pilot and helicopter to return from a prior task. After the pilot arrived, they completed the operator’s online induction and a safety brief with the pilot and then briefed the pilot on their plan for the weed survey.
None of the officers had previously met the pilot who they understood was new to the company and had not previously done the English Broom weed survey task with them. They reported that the pilot was operating in a cautious manner and appeared to be safety‑conscious, advising them all to speak-up if they identified any hazards during the flight. On departure, the pilot made a radio call to their NPWS contact for flight‑following purposes, and they conducted a hazard identification for wires during the flight upstream to the Guthega Power Station.
Persons permitted on board during aerial work operations
For aerial work operations conducted under Part 138, CASA advisory circular 138-01 specified that persons who were permitted on board must be categorised as either:
crew members (including flight crew, air crew and task specialists)
passengers that meet the requirement to be aerial work passengers.
The advisory circular further defined an air crew member, task specialist and aerial work passenger as:
Air crew member
An air crew member…includes crew members who carry out a function during the flight relating to the safety of the aircraft.
Task specialist
A task specialist … includes crew members who carry out a function for the flight relating to the aerial work operation (as distinct from a safety related role).
Examples of a task specialist would include a camera operator that operates an external camera pod, or an aerial shooter used in an animal culling operation.
A task specialist will require training to be inducted into the operation and to ensure they are competent in carrying out their assigned function as a member of the operator's crew.
Aerial work passenger
…are persons who are closely associated with the purpose of the aerial work operation. Their presence in the aircraft must not be for mere convenience or enjoyment.
Examples of such persons would include: Personnel involved in carrying out or supporting a mustering activity carried on a positioning flight before or after the mustering operation, such as ground based personnel to assist with refuelling or for opening and closing of gates etc. and yarding of stock for the mustering operation…
In most circumstances aerial work passengers do not require training before their carriage on an aerial work operation or a positioning flight, but they will in all cases (except for some notable situations, such as a person being rescued) require a safety briefing prior to the flight...
On the accident day, as the helicopter was being used to conduct a low-level weed survey activity, it met the definition of a task specialist operation. In terms of the roles as defined above, the pilot was the only flight crew member and there were no air crew members. The 3 NPWS officers with the roles of task coordinator and primary observers would be classed as task specialists. While the area ranger assisted with the task, they reported that they were on the flight as an opportunity for familiarisation of the survey area.
Operational hazards
CASA flight crew licencing uses a competency-based training and assessment system for pilots. Various competencies are required to be demonstrated by pilots during both initial and recurrent licence testing. The competencies vary by aircraft type and licence type.
For pilots to achieve their helicopter rating, they are required to demonstrate that they have the skills and underpinning knowledge to manage abnormal and emergency situations in helicopters (CASA, 2021c). The range of situations include, but are not limited to:
key hazards – underpinning knowledge of their causal factors, contributing operational situations, avoidance and recognition of symptoms and recovery techniques that include:
the impact of high gross weight and high-density altitude on key hazards
techniques for how to avoid a potentially hazardous situation whilst in flight.
These competencies were consistent with the list of hazards detailed in the jointly developed CASA and Civil Aviation Authority of New Zealand helicopter flight instructor manual, issue 3 (CASA, 2012). The instructor manual differentiated hazards from emergencies, which are the technical failures particular to the helicopter model and addressed in the flight manual emergency procedures section.
To be licensed for low-level helicopter operations, pilots must demonstrate skills to safely conduct low‑level operations include managing variable terrain and weather, surface conditions, loose objects and personnel. The required underpinning knowledge related to critical operational conditions that included retreating blade stall,[17] vortex ring state, over pitching and loss of anti‑torque or tail rotor effectiveness (CASA, 2021c).
The ATSB reviewed the emergencies and hazards chapter of the FAA Helicopter Flying Handbook (2019) and found key operational hazards presented were the same as those that CASA required pilots to demonstrate. The FAA handbook provided a thorough description of each of the key hazards, which included techniques for avoidance and recovery. The FAA handbook also reported the following about LTE events:
Certain flight activities lend themselves to being more at high risk to LTE than others. For example, power line and pipeline patrol sectors, low-speed aerial filming/photography as well as in the Police and Helicopter Emergency Medical Services (EMS) environments can find themselves in low and slow situations over geographical areas where the exact wind speed and direction are hard to determine.
Loss of tail rotor effectiveness
Introduction
Loss of tail rotor effectiveness (LTE) or unanticipated yaw is a phenomenon that can occur in single main rotor, tail rotor-equipped helicopters. It is a condition that occurs when the air flow through a tail rotor is changed in some way, by altering the angle or speed at which the air passes through the rotating blades of the tail rotor disc (FAA, 2019). If uncorrected, LTE can result in loss of control of the helicopter and serious to fatal occupant injuries. In 1995, the FAA published advisory circular 90-95 Unanticipated right yaw in helicopters, which described a loss of tail rotor effectiveness as:
…a critical, low-speed aerodynamic flight characteristic which can result in an uncommanded rapid yaw rate which does not subside of its own accord and, if not corrected, can result in the loss of aircraft control.
Any manoeuvre which requires the pilot to operate in a high-power, low-airspeed environment with a left crosswind or tailwind creates an environment where unanticipated right yaw may occur.
LTE is not related to a maintenance malfunction and may occur in varying degrees in all single main rotor helicopters at airspeeds less than 30 knots.
Single-rotor helicopters manufactured in the US, such as the Bell 206, have main rotors that rotate anticlockwise when viewed from above. When powered, their rotation produces a torque reaction or tendency of the helicopter to turn in the opposite direction, which is a right yawing motion from the pilot’s view. The tail rotor thrust provides the anti‑torque control. An effective tail rotor relies on a stable and relatively undisturbed airflow in order to provide a steady and constant anti-torque reaction (FAA, 2019).
The FAA AC described 3 wind conditions conducive to the onset of LTE. One of these conditions refers to the relative wind[18] azimuth of 285° to 315°, which can produce ‘main rotor disc vortex interference’ with the tail rotor (Figure 8) and is described as:
As the main rotor vortex passes the tail rotor, the tail rotor angle of attack is reduced. The reduction in the angle of attack causes a reduction in thrust and a right yaw acceleration begins. The thrust reduction will occur suddenly and, if uncorrected, will develop into an uncontrollable rapid rotation about the [main rotor] mast.
The relative wind from the critical quadrant may present when the nose of the helicopter is pointing forward (Figure 8), or the condition is generated when the helicopter is flown with the nose sufficiently yawed to the right.
Figure 8: Main rotor disc vortex interference with tail rotor
Source: FAA Helicopter Flying Handbook (FAA, 2019), annotated by the ATSB
Factors affecting loss of tail rotor effectiveness
Other than main rotor blade action affecting the quality of the airflow about the tail rotor disc and impacting its ability to provide useful thrust, additional factors are also considered when discussing LTE. According to the FAA Helicopter Flying Handbook (2019):
The design of main and tail rotor blades and the tailboom assembly can affect the characteristics and susceptibility of LTE but will not nullify the phenomenon entirely.
FAA AC 90-95 also identifies other factors that influence the severity of the onset of LTE including:
Gross Weight and Density Altitude. An increase in either of these factors will decrease the power margin between the maximum power available and the power required to hover. The pilot should conduct low-level, low-airspeed manoeuvres with minimum weight.
Recovery technique
The Bell 206L-1 rotorcraft flight manual revision 14 did not have an emergency procedure for LTE but did have a procedure for a complete loss of thrust under the heading tail rotor control failure, which was a mechanical failure. Following the procedure for a complete loss of thrust, pilots were to reduce the throttle to idle and immediately enter an autorotation while maintaining a minimum airspeed of 52 kt during the descent.
The FAA AC 90-95 recommended recovery technique from LTE was:
a. If a sudden unanticipated right yaw occurs, the pilot should perform the following:
(1) Apply full left pedal. Simultaneously, move cyclic[19] forward to increase speed. If altitude permits, reduce power.
(2) As recovery is effected, adjust controls for normal forward flight.
b. Collective[20] pitch reduction will aid in arresting the yaw rate but may cause an increase in the rate of descent. Any large, rapid increase in collective to prevent ground or obstacle contact may further increase the yaw rate and decrease rotor rpm.
c. The amount of collective reduction should be based on the height above obstructions or surface, gross weight of the aircraft, and the existing atmospheric conditions.
d. If the rotation cannot be stopped and ground contact is imminent, an autorotation may be the best course of action. The pilot should maintain full left pedal until rotation stops, then adjust to maintain heading.
Heli Surveys operations manual
The Heli Surveys Operations Manual volume 10 – Specialist operations, prescribed the operator’s general low flying requirements. Paragraph 0.7.3, under Conduct of flight during low flying stated the following:
Pilots shall be aware of recovery techniques and avoid flight configurations which could include:
• Vortex ring/ settling with power.
• Tail rotor vortex ring or loss of tail rotor effectiveness.
• Downwind operations outside the aircraft performance envelope.
• Loss of close visual cues to indicate actual aircraft relative movement and out of wind operations (particularly over water), leading to possible unanticipated control difficulties.
The operations manual did not include any avoidance or recovery procedures for LTE nor any reference material to address this condition.
Safety risk management
Aerial work risk management
Pre-operational risk assessment
CASR Part 138 required an operator conducting aerial work to undertake risk assessments of its operations. The Part 138 MOS and corresponding advisory circular (AC 138-05 v1.1) detailed a layered approach to risk assessments. One of the key requirements was that an operator should undertake an overarching assessment (pre‑operational risk assessment) to consider and evaluate the risks associated with its proposed operations, in this case, low-level helicopter survey. This assessment recognised the underlying principles of CASR Part 138, where the risks and hazards associated with a type of aerial work operation are common to that type of operation. The MOS indicated that the matters to be considered for such an assessment included:
• the operation and its particular characteristics
• the location of the operation and its particular characteristics
• the aircraft to be used in the operation, its particular characteristics, and its performance
• the qualifications and experience of the crew members to be used in the operation
• the hazards, external to the aircraft, that may be met in the course of the operation.
The operator is required to gather data for inclusion in the pre-operational risk assessment using a range of sources. Acknowledging that certain risk factors may be common to all operators, may be particular to the aircraft type operated or may be unique to the operator; potential sources include, but are not limited to (CASA, 2021b):
CASA ‘sector risk profiles’ for the varying types of operations
ATSB incident and accident reports
industry association safety reports
manufacturers' safety bulletins and advisory notices
input from experienced pilots and other operators.
Once the pre-operational risk assessment has been populated, it should be updated over time to include lessons learnt from previous operations. It should also form part of the operator’s operations manual.
Flight risk management plan
The results of the pre-operational risk assessment were to be considered when preparing the flight risk management plan, which was specific to an individual flight or task within the type of operation. The plan should outline the specific mitigators or risk controls that were to be used during the flights.
Pre-flight risk review
The next step was for the pilot, on behalf of the operator, to conduct a pre-flight risk review, with reference to the pre‑operational risk assessment, flight risk management plan, and the most recent data for the operation. The review was to be completed prior to the commencement of the operation and was to consider the conditions and circumstances that existed at the site or area at the time of the proposed activities. This ensured that the operation could be conducted without unacceptable safety risk.
Operator risk management
As per CASR Part 138, Heli Surveys was required to undertake risk assessment and mitigation processes and include those processes in its suite of operational documents. The Heli Surveys Operations Manual described that the operator would address its risk management obligations via the use of Safe Work Method Statements (SWMS).
The Heli Surveys Safety Management Systems Manual further detailed how risk was identified, controlled and documented. Their safety risk management process started with hazard identification, which included internal sources and external sources. A hazard was defined in their SWMS as ‘what could result in harm’ and was used to describe both the hazard and associated risk.
Internal sources for hazard identification included, but were not limited to:
safety assessments of systems and operations
voluntary and mandatory safety reports
inspections and audits.
Its list of external sources included, but was not limited to:
accident and incident reports
safety information bulletins, safety alerts and other safety publications from CASA, Airservices Australia, the ATSB and other authorities worldwide.
The operator had prepared SWMSs to comply with the CASR Part 138 requirements which was equivalent to a pre-operational risk assessment. As the accident flight was a low‑level survey operation in the Snowy Mountains, the 2 SWMS relevant to the flight were Low level surveys and aerial photography (henceforth referred to as Low-level surveys) and Alpine operations.
The SWMS documents provided the means to record the specific tasking event, the equipment and approvals that were relevant, and any specific checks or personal protective equipment required to perform the task. A risk matrix was also included. The risk matrix described the likelihood and consequence of each identified hazard and provided the means to assess the initial and residual risk level following the implementation of suitable risk controls.
The ATSB reviewed the SWMSs that were developed by the operator. A summary of the internal and external hazards that were identified by the operator are below (Table 1).
Table 1: Summary of hazards related to Safe Work Method Statements for low-level survey tasking and alpine operations
Low-level survey hazards
Alpine operations hazards
intercom failure
adverse weather events
high communication workload/distraction
inadvertent flight into instrument meteorological conditions
loose articles exiting aircraft
collision with powerlines/aerials
collision with objects while airborne
heavy landing – exceeding power requirements
inadvertent flight into instrument meteorological conditions
exposure – inappropriate dress for conditions
restraint harness issues
aircraft door issue
turbulence/windshear
The heavy landing hazard associated with the alpine operations SWMS was assessed by the ATSB to be related to the CASA flight crew licensing competency requirement to manage the hazard associated with overpitching. The SWMS provided some control measures, such as a power check, landing into wind and monitoring environmental conditions between a landing and take-off.
With the exception of the relationship between overpitching and the operator’s heavy landing hazard in its alpine operations SWMS, the ATSB did not find references to hazards associated with abnormal situations and emergencies specific to the operator’s unique activities in its SWMS. Of note, there was no reference to LTE and vortex ring state, and the impact of flight regimes and operations at high gross weights and density altitudes that may affect such hazards.
The operator reported that pilots were required to have read and understood the suite of SWMS documents, which were provided during their induction process and at scheduled intervals thereafter. However, there was no requirement for pilots to conduct a pre-flight risk review for low-level survey operations and reference the relevant SWMS when conducting pre-flight tasks in preparation for the activity. As such, the pilot had not conducted a review prior to the accident flight.
Client risk management
The NPWS (the client) had contracted Heli Surveys to conduct the weed survey operation. Its Aviation Safety Policy and related documents were provided to the ATSB. The policy identified a range of aviation operations that utilised rotary wing aircraft.
The policy adopted a risk management approach to aviation operations and safety. Key elements of the policy were the development and observance of aviation‑related standard operating procedures and the use of a job safety analysis (JSA).[21] The JSA assessed the risks associated with each task, which was equivalent to a flight risk management plan.
Regarding vegetation‑related activities that necessitated low-level flight operations, the NPWS provided several task-related JSA documents that identified specific hazards. The documents also detailed the control measures to be implemented to manage the associated risks. The JSA documents that were provided related to low-level flying in general, low-level flying when undertaking Scotch (English) Broom survey and aerial application (spraying) activities.
When engaging in those activities, a key control measure specified in the JSA advised that only ‘essential personnel’ were to be on board the operating helicopter. The NPWS reported that the suite of documents supporting aviation operations did not provide a definition of essential personnel nor was there a procedure on record that detailed the roles and responsibilities of NPWS personnel reflected in the JSA control measure.
Related occurrences
Loss of tail rotor effectiveness
Between 2013 and 2022, the ATSB received 16 notifications where the reporter advised of an LTE or unanticipated yaw event. Of the 16 notifications, 12 were investigated by the ATSB. Most of these resulted in nil to minor injuries to those involved and one serious injury and one fatality. Some of these investigations are described below.
On 19 January 2013, a Bell 206B3 helicopter was being operated on an aerial filming task over hilly terrain on the north-eastern outskirts of Perth, Western Australia. After hovering and manoeuvring at about 500 ft above ground level to allow the camera operator to record footage of a truck accident, the pilot conducted a right orbit to complete filming and depart the area. The pilot had initiated the turn when the nose of the helicopter moved left, then suddenly and rapidly to the right as the helicopter yawed and developed a rotation of about 5 revolutions.
The ATSB found that, when the pilot turned to the right to commence the orbit, the helicopter was exposed to a crosswind from the left while at an airspeed around the 30 kt threshold value for susceptibility to LTE, precipitating an unanticipated right yaw and temporary loss of control. The pilot regained sufficient control for a forced landing.
On 20 July 2015, the pilot of a Bell 206L3 (LongRanger) helicopter, registered VH-BLV, conducted a charter flight from Essendon Airport to Falls Creek, Victoria, with 5 passengers on board. The helicopter took off from Essendon close to its maximum take‑off weight.
When at 700 ft above ground level and tracking from the north-west, the pilot conducted a shallow approach towards the helipad at Falls Creek. As the helicopter descended to about 50 ft above ground level, the pilot found that significantly more power was required to conduct the approach than anticipated. The pilot assessed that there was insufficient power available to continue to land and elected to abort the approach. The pilot pushed forward on the cyclic to increase the helicopter’s airspeed and conducted a left turn.
As the helicopter turned left, it started to yaw rapidly towards the right. The pilot applied full left anti-torque pedal to counteract the yaw, but the helicopter continued to yaw. The helicopter turned through one and a half revolutions, as the pilot lowered the collective. Lowering the collective reduced the power demand of the power rotor system, thereby increasing the ability of the anti‑torque pedals to stop the right yaw. The combination of lowering collective and applying forward cyclic to gain forward airspeed, allowed the pilot to regain control of the helicopter. The pilot then conducted a left turn towards the helipad and made an approach to the helipad from an easterly direction. The helicopter landed following the second approach without further incident.
The ATSB’s report highlighted the importance for pilots to understand and avoid conditions that are conducive to unanticipated yaw or LTE and noted that pilots can reduce their exposure to LTE by maintaining awareness of the wind and its effect on the helicopter. Further, if a pilot encounters unanticipated yaw, quick application of the correct response is essential to recover control of the helicopter.
On 28 January 2019, the crew of a Sikorsky S-64E Skycrane helicopter was conducting firebombing activities when it collided with water at Woods Creek Dam, Victoria. The collision occurred following an approach to the dam to fill an external tank with water. The helicopter was crewed by 2 pilots, and a maintenance crew chief was also on board. Following the collision, all the occupants were able to exit the helicopter and swim to shore. One crewmember was seriously injured and 2 were uninjured. The helicopter was substantially damaged.
The ATSB found that the helicopter was placed in a steep flare, which contributed to the helicopter entering vortex ring state when on approach to the dam.
It was also noted that the operator’s operations manual stated that only flight crew and crew essential to the operation could be carried aboard the aircraft during firefighting operations. The operation could be conducted without the crew chief, and not all company crew chiefs were on board their aircraft during firefighting operations. While the crew chief had significant system and task knowledge, they were not required to be on board the helicopter.
On this occasion, their presence on board subjected them to the significant hazards associated with underwater egress. More generally, the carriage of additional personnel during specialised operations like firefighting exposes them to unnecessary risk.
On 21 May 2019, while engaged in a planned cull of feral animals in Kakadu National Park, Northern Territory, a crew of 3 were using a Bell 206B3 JetRanger helicopter for aerial platform shooting. While the helicopter was operating at about 50 ft above the ground, the engine decelerated to idle, resulting in an immediate loss of power, and subsequent collision with terrain. The 3 occupants (pilot, shooter and spotter) were seriously injured.
The investigation identified that it was normal practice across industry that an aerial culling task was performed with just 2 persons on board the helicopter, the pilot and a shooter. Experienced aerial shooters interviewed after the accident expressed a preference for carrying just the pilot and shooter on board to reduce risk to crew, carry more fuel to improve endurance and to complete more work. In 2016, the aerial culling task was redesigned for 3 crew, including a spotter. There was no formal risk analysis of the inclusion of the spotter position, or consideration of the potential benefits of improved data collection when weighed against operational difficulties in recording data, reduced efficiencies in operation, and increased exposure of employees to risk.
The investigation identified that, given the increased complexity and risk in low-level operations, the number of crew should be kept to a minimum. That is, only personnel essential for conducting the task should be carried.
Safety analysis
Introduction
On the morning of 11 March 2022, a Bell B206L-1 helicopter, registered VH-BHF, departed Jindabyne aerodrome, New South Wales, to conduct a weed survey task on behalf of the National Parks and Wildlife Service (NPWS). On board were the pilot and 4 NPWS officers. While descending towards the riverbed in the vicinity of the Guthega power station, the helicopter started an uncommanded yaw to the right. The pilot was able to stop the yaw but was unable to arrest the descent before the helicopter collided with terrain. The helicopter was destroyed. Three occupants received serious injuries, and the remaining 2 occupants received minor injuries.
The following analysis will discuss the uncommanded yaw, and the carriage of persons on the flight. It will also consider the risk management practices of both the operator and its client and discuss the emergency response following notification of the accident.
Helicopter position
The weed survey task was a low-level, low-speed flight activity. On the accident flight, in addition to the pilot seated in the front right seat, there was an NPWS officer in the front left seat and 3 NPWS officers in the cabin area with 2 seated on the left of the helicopter. With 3 of the NPWS officers seated on the left, the pilot was asked if the helicopter could be flown sideways to provide the best view of the target vegetation for those officers. In response, the pilot yawed the helicopter about 45° to the right of their track. Forward flight with the helicopter yawed 45° to the right, in calm wind conditions, produced a relative wind opposite to the motion of the helicopter, from an angle of about 315°.
Weight and balance data indicated that with the 5 occupants on board, the helicopter was operating within 100 kg of its maximum all-up weight. It was also operating at a density altitude of about 4,500 ft. As weight and density altitude increase, the margin between the power available and power required for the flight is reduced. Further, the flight data identified that the groundspeed of the helicopter was below 25 kt and further reduced to less than 20 kt for several seconds prior to the uncommanded right yaw. As there was little wind, the airspeed was close to the recorded groundspeed.
As described by the United States Federal Aviation Administration in its Helicopter Flying Handbook and advisory circular 90-95, there are certain conditions that can change the air flow through a tail rotor, subsequently resulting in a loss of tail rotor effectiveness (LTE). In this case, the combination of a low speed and right yaw placed the helicopter inside the region of main rotor disc vortex interference with the tail rotor, a condition conducive to the onset of LTE. The severity of the onset of LTE was further influenced by the high gross weight and density altitude.
Contributing factor
The sideways movement of the helicopter during the weed survey operation, combined with the high-density altitude, high gross weight, and low airspeed, were conditions conducive to the onset of a loss of tail rotor effectiveness.
Loss of tail rotor effectiveness
The pilot’s description of flying the helicopter with a significant amount of right yaw at about 30 kt was consistent with the recorded data at the start of their run from the Guthega power station. However, the speed slowly decayed below 20 kt just prior to an uncommanded right yaw when the pilot applied some left anti-torque pedal to straighten the helicopter and improve their vision on their approach to the river below. After the helicopter started yawing to the right, the pilot identified a forced landing site in the river and rolled the throttle back to idle, which stopped the yawing motion. The cessation of the yawing motion when the engine power was reduced indicated the yaw was being driven by the reaction to the engine torque applied to the main gearbox and there was insufficient anti-torque to prevent it.
The ATSB determined that there was no evidence of a pre-existing mechanical issue, and the helicopter had the performance capability to operate at the altitude of the survey area. However, the helicopter was positioned in the region of main rotor disc vortex interference with the tail rotor just prior to the loss of control. As such, the ATSB concluded that the uncommanded right yaw was likely an LTE event.
At the time of the event, the helicopter was operating at about 150 ft above ground level in the avoid area of the height-velocity diagram, in addition to which, it was also outside the weight-density altitude limits for the height‑velocity diagram. Therefore, there was no assurance a safe forced landing with minimal damage and injuries could be achieved from the height that the autorotation was commenced.
Contributing factor
It was likely that a loss of tail rotor effectiveness occurred at a height that was insufficient for the pilot to recover before the helicopter impacted the ground.
Operator’s risk management
As a Part 138 operator, Heli Surveys was required to adopt a layered approach to risk management. This approach included conducting a pre-operational risk assessment, which considered all the generic risks and hazards common to the type of operation, in this case, low‑level survey. Heli Surveys achieved this requirement through the Safe Work Method Statements (SWMS).
To inform the pre-operational risk assessment, a range of internal and external data sources could be used that considered the risks common to all low-level survey operators, particular to the aircraft type operated, or unique to the operator. For example, for low-level helicopter operations this may include hazards such as a high-density altitude, retreating blade stall, LTE, vortex ring state and over pitching. Therefore, it was foreseeable that hazards influenced by the particular operating environment would be included in the operator’s SWMS for both Low-level surveys and Alpine operations.
The ATSB reviewed the SWMS accounting for the circumstances of the accident. The SWMS incorporated heavy landings, adverse weather events, collisions with obstacles and hazards associated with the carriage of passengers and task specialists. In consideration of the operation and activities, which included the carriage of passengers and task specialists, the hazards identified by the operator appeared to be relevant. However, their SWMS did not address LTE, although this was identified in its operations manual as a condition specific to low flying and is a known hazard as discussed by the Civil Aviation Safety Authority and the United States Federal Aviation Administration.
The English Broom weed survey operation was conducted at low level and low speed, which were conditions conducive to the onset of LTE. Therefore, and in establishing the context for the operation, LTE was relevant. However, while the risk of LTE was not considered in the SWMS, the accident pilot was familiar with LTE and indicated that it had been covered in their training at some point. As a result, the ATSB was unable to determine if having LTE identified in the SWMS would have influenced the accident outcome. That said, the absence of this consideration did not allow for formal mitigation strategies to be implemented, nor provide assurance that the risk level associated with LTE was as low as reasonably practical. Consequently, there was a reliance on the underpinning knowledge and operational experience of the individual pilot to manage the risk of LTE.
In addition, as a requirement for Part 138 operators, the pre-operational risk assessment, or in this case the SWMS, was to inform the pre-flight risk review. This review was to be performed by a pilot, on behalf of the operator, before a flight commenced. The operator reported that such a review was not conducted for its low-level survey operations nor was one performed by the accident pilot. The merits of this process would have provided the operator an opportunity to validate the SWMS against the proposed operation and allow pilots to determine that the operation could be conducted without unacceptable safety risk.
Documenting and detailing known hazards and the associated risk controls in a dedicated SWMS, reviewed pre-flight, would complement a pilot’s underpinning knowledge. In turn, this would raise immediate awareness of the possibility of encountering hazards such as LTE when conducting a low-level survey task. Further, the pre-flight risk review would provide the means for all the participants involved to consider these critical operational conditions and associated controls. This would complement the safety briefing provided by the pilot in conjunction with the NPWS officers as they prepared for the accident flight.
Other factor that increased risk
The Heli Surveys safe work method statements for low-level survey and alpine operations did not identify the operational factors that could affect the control of the helicopter. There was also no requirement for its pilots to conduct a pre‑flight risk review for low-level survey operations. Combined, this limited the operator’s ability to manage the possibility of loss of tail rotor effectiveness and ensure that the risks associated with low-level survey operations were as low as reasonably practicable. (Safety issue)
Helicopter occupants
There were 5 occupants on the helicopter, including the pilot. It was very likely that the weed survey could have been completed with just the NPWS coordinator in the front left seat and 2 officers in the left and right rear forward‑facing seats. As such, they would meet the criteria of a task specialist as described under Part 138. If not required as a task specialist, and excluding the pilot, all others on board would be regarded as aerial work passengers and would not be permitted. As such, it was likely that the additional NPWS officer on board (the area ranger) was not fulfilling the role of a task specialist. The additional person’s presence appeared to be motivated by opportunity, and while it was acknowledged that they could contribute as a survey team member, their involvement was not essential to a successful task outcome.
Given the nature of the task and the operating conditions under which it was being conducted, the inclusion of personnel who were not essential to fulfilling the task outcomes exposed them to the risks of low-level helicopter flight and, in the event of an accident or incident, potential injury. On this occasion, the occupant who did not have a specific role to perform, for either the spotting or logging activity, was seriously injured in the accident when operating at low level with limited landing options available due to the surrounding terrain.
Contributing factor
The carriage of an additional person on board the helicopter who was not essential to the tasking, exposed them to risks associated with low flying operations over inhospitable terrain.
Client’s risk management
The client (NPWS) arranged for the survey flight to be undertaken, and its officers presented at Jindabyne to board the helicopter on the appointed day. Risk assessments covering low-level flying operations and weed survey tasks in the form of a job safety analysis were on record, and a key risk control measure advised that only essential personnel were to be on board. However, no definition of essential personnel was available to potentially limit the number of persons that would be exposed to the identified risks. Defining essential personnel would also support informed distinctions between those who would appropriately fulfil roles as task specialists and those who were aerial work passengers.
Further, the procedure and roles of the persons conducting the survey were not documented. This likely allowed a degree of discretion to be applied by the participants, which resulted in others participating alongside task specialist(s) whose presence may, on occasion, be unnecessary. For example, for this accident one of the NPWS officers who did not have a specific role received serious injuries.
The client was also engaged in other activities such as aerial spraying and culling, both of which likely involved helicopter operations at low level. Having a definition of essential personnel and documenting their respective roles and responsibilities as task specialists would provide the necessary information for determining who should be involved. This would potentially confine the numbers to the minimum required to conduct the task thereby minimising risk exposure.
Contributing factor
The New South Wales National Parks and Wildlife Service operating procedures referred to, but did not define ‘essential personnel’, or specify their roles and responsibilities as task specialists when performing aerial work activities. (Safety issue)
Accident notification
The helicopter was equipped with a fixed emergency locator transmitter and an electronic flight tracking device (TracPlus), which provided active monitoring of the helicopter’s position. Additionally, a personal locator beacon and a satellite phone were carried on board as part of the operator’s survival kit.
Within a very short time of the accident occurring there were reports of the helicopter's fixed emergency locator transmitter activating, the TracPlus unit transmitting the helicopter’s last recorded position and manual activation of a personal locator beacon. The multiple reports removed any doubt of a spurious transmission from any of the units and, as a result, the operator and emergency services were able to respond with minimal delay.
The timely alerts also provided the means for the power station to be alerted to the presence of injured persons on the riverbank who required urgent medical assistance. Their recovery would likely have been impacted by an increase in water level and provided the opportunity for decisions to be made regarding water discharge into the river via the power station.
The extraction of the damaged helicopter from the Snowy River was also influenced following advice of water storage buildup and possible uncontrolled discharge from the Guthega Dam spillway. The early notification likely provided sufficient time to plan for and safely airlift the helicopter wreckage from the river for detailed examination and removed a potential environmental issue.
Other finding
The activation of the on-board emergency locator transmitter and a flight monitoring device, and manual activation of a personal locator beacon, resulted in an immediate emergency response.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision with terrain involving Bell 206L-1, VH-BHF, 20 km north-west of Jindabyne, New South Wales, on 11 March 2022.
Contributing factors
The sideways movement of the helicopter during the weed survey operation, combined with the high-density altitude, high gross weight, and low airspeed, were conditions conducive to the onset of a loss of tail rotor effectiveness.
It was likely that a loss of tail rotor effectiveness occurred at a height that was insufficient for the pilot to recover before the helicopter impacted the ground.
The carriage of an additional person on board the helicopter who was not essential to the tasking, exposed them to risks associated with low flying operations.
The New South Wales National Parks and Wildlife Service operating procedures referred to, but did not define ‘essential personnel’, or specify their roles and responsibilities as task specialists when performing aerial work activities. (Safety issue)
Other factors that increased risk
The Heli Surveys safe work method statements for low-level survey and alpine operations did not identify the operational factors that could affect the control of the helicopter. There was also no requirement for its pilots to conduct a pre‑flight risk review for low-level survey operations. Combined, this limited the operator’s ability to manage the possibility of loss of tail rotor effectiveness and ensure that the risks associated with low-level survey operations were as low as reasonably practicable. (Safety issue)
Other findings
The activation of the on-board emergency locator transmitter and a flight monitoring device, and manual activation of a personal locator beacon, resulted in an immediate emergency response.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out or are planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: The Heli Surveys Safe Work Method Statements for low-level survey and alpine operations did not identify the operational factors that could affect the control of the helicopter. There was also no requirement for its pilots to conduct a pre-flight risk review for low-level survey operations. Combined, this limited the operator’s ability to manage the possibility of loss of tail rotor effectiveness and ensure that the risks associated with low‑level survey operations were as low as reasonably practicable.
Safety issue description: The New South Wales National Parks and Wildlife Service operating procedures referred to, but did not define, ‘essential personnel’, or specify their roles and responsibilities as task specialists when performing aerial work activities.
Safety action not associated with an identified safety issue
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Additional safety action taken by Heli Surveys
In addition to the safety action detailed above, Heli Surveys has revised its risk register detailing both flight-based and ground‑based threats in its operations and associated risk controls. It has also introduced a ‘Hazardous Flight Conditions’ ground-based course that was proactively developed in response to this accident. The intent of the course was to refamiliarize pilots with such conditions (for example, loss of tail rotor effectiveness) to ensure currency and assist with informed decision‑making and is to be completed every 12 months. The flying aspects discussed in the course will be covered in operator proficiency checks.
Additionally, Heli Surveys has defined ‘essential crew’ in its operations manual. It has also added a requirement that, prior to flight, the pilot in command is to confirm that when undertaking Part 138 operations, all persons on board are deemed essential and each person has a relevant and specific task.
Glossary
AC
Advisory circular
CASA
Civil Aviation Safety Authority
CASR
Civil Aviation Safety Regulations
ELT
Emergency locator transmitter
FAA
Federal Aviation Administration (United States)
HOFO
Head of flying operations
JSA
Job safety analysis
LTE
Loss of tail rotor effectiveness
NPWS
National Parks and Wildlife Service
MOS
Manual of Standards
PLB
Personal locator beacon
SWMS
Safe Work Method Statement
Sources and submissions
Sources of information
The sources of information during the investigation included:
the pilot
New South Wales National Parks and Wildlife Service officers
Heli Surveys Pty Ltd
New South Wales National Parks and Wildlife Service
Bureau of Meteorology
Civil Aviation Safety Authority
New South Wales Police Force
recorded data – TracPlus unit.
References
ATSB. (2013). A review of the effectiveness of emergency locator transmitters in aviation accidents (AR-2012-128). Australian Transport Safety Bureau, Canberra, ACT, Australia.
CASA. (2021c). Part 61 Manual of Standards Instrument 2014. Civil Aviation Safety Authority, Canberra, ACT, Australia.
CASA. (2021d). Part 91 (General Operating and Flight Rules) Manual of Standards 2020. Civil Aviation Safety Authority, Canberra, ACT, Australia.
CASA. (2021e). Part 138 (Aerial Work Operations) Manual of Standards 2020. Civil Aviation Safety Authority, Canberra, ACT, Australia.
CASA. (2021f). Acceptable means of compliance and guidance material, (Aerial work operations - Part 138 of CASR). Civil Aviation Safety Authority, Canberra, ACT, Australia.
CASA. (2023). Multi-part Advisory Circular: AC 91-30, AC 121-12, AC 133-03 and AC 135-14 V1.0, Emergency locator transmitters. Civil Aviation Safety Authority, Canberra, ACT, Australia.
FAA. (1995). Advisory Circular: Unanticipated right yaw in helicopters (AC 90-95). U.S. Department of Transportation, Federal Aviation Administration, Washington, D.C., USA.
FAA. (2019). Helicopter Flying Handbook (FAA-H-8083-21B). U.S. Department of Transportation, Federal Aviation Administration, Oklahoma City, OK, USA.
NTSB. (2017). Safety Alert SA-062: Loss of tail rotor effectiveness in helicopters. National Transportation Safety Board, Washington, D.C. USA.
Weeds Australia. (2019). Broom, English Broom, Scotch Broom, Common Broom, Scottish Broom, Spanish Broom,www.weeds.org.au accessed July 2024.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
pilot of the accident flight
Heli Surveys Pty Ltd
National Parks and Wildlife Service officers
National Parks and Wildlife Service
Civil Aviation Safety Authority
Transportation Safety Board of Canada.
Submissions to the report were received from the following parties:
Civil Aviation Safety Authority
Heli Surveys Pty Ltd
National Parks and Wildlife Service
National Parks and Wildlife Service officers.
The submissions were reviewed and where appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
About ATSB reports
ATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines.
Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner.
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence.
The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau.
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1]English Broom: also known as Broom, Scotch Broom, Common Broom or Spanish Broom and is a highly invasive, environmental weed of national significance that favours cooler, higher rainfall regions.
[2]Officers: denotes NPWS personnel and their job titles and includes officers, rangers and other staff members.
[3]Anti-torque control pedals: a primary helicopter flight control that changes the pitch of tail rotor blades to control thrust around the yaw axis. Acts to counterbalance the main rotor torque reaction and provides heading control in the hover and balanced flight when the helicopter is in forward motion.
[4]Yaw: the motion of an aircraft about its vertical or normal axis.
[5]Autorotation: a condition of descending flight where, following engine failure or deliberate disengagement, the rotor blades are driven solely by aerodynamic forces resulting from rate of descent airflow through the rotor. The rate of descent is determined mainly by airspeed.
[6]The operator reported that, as the registered owner of the beacons, the Australian Maritime Safety Authority contacted the nominated person and the head of flying operations was subsequently advised of the beacon activations.
[7]Visual flight rules: a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to allow the pilot to see where the aircraft is going.
[8]Cloud cover: in aviation, cloud cover is reported using words that denote the extent of the cover – ‘scattered’ indicates that cloud is covering between a quarter and a half of the sky.
[9]QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean seal level.
[10]The force needed to accelerate a mass. G-force is normally expressed in multiples of gravitational acceleration (normal gravity = 1g).
[11]For flight operations at low airspeeds, there is a negligible difference between calibrated and indicated airspeed.
[12]The height-velocity diagram shows the combinations of indicated airspeed and height above the ground which will allow an average pilot to successfully complete a landing after an engine failure. By carefully studying the height-velocity diagram a pilot can avoid the combinations of altitude and airspeed that may not allow sufficient time or altitude to enter a stabilised autorotative descent (FAA, 2019).
[13]As of July 2025, the carriage of fireground personnel was also classified as an aerial work operation core activity.
[14]Vortex ring state describes an aerodynamic condition where a helicopter may be in a vertical descent with 20% up to maximum power applied, and little or no climb performance (FAA, 2019).
[15] Overpitching occurs when collective pitch is increased to a point where the main rotor blade angle of attack creates so much drag that all available engine power cannot maintain or restore normal operational revolutions per minute (ICAO, 2024).
[16]When a helicopter is hovering, some of the air passing through the main rotor disc is recirculated back into the disc from the top. This phenomenon is common to all airfoils and is known as tip vortices. As long as the tip vortices are small, their only effect is a small loss in rotor efficiency. However, operating in close proximity to obstructions can lead to an increase in recirculation and loss of performance (FAA, 2019).
[17]In forward flight, the relative airflow through the main rotor disc is different on the advancing and retreating side of the rotor blades. The relative airflow over the advancing side is higher due to the forward speed of the helicopter, while the relative airflow on the retreating side is lower. To generate the same amount of lift across the rotor disc, the advancing blade flaps up while the retreating blade flaps down. This causes the angle of attack to increase on the retreating blade, which increases lift. At some point, as forward speed increases, the low blade speed on the retreating blade, and its high angle of attack will result in a stall and loss of lift (FAA, 2019).
[18]Relative wind: the airflow relative to an aerofoil created by movement of an aerofoil through the air.
[19]Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.
[20]Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.
[21]Job safety analysis: a form of risk assessment that details, step-by-step, how a task is to be performed safely.
The ATSB conducts 'no-blame' investigations for the purpose of improving transport safety. ATSB investigations are independent of other investigations, including those conducted by the Civil Aviation Safety Authority and the Northern Territory Police Force.
What happened
On 28 February 2022, at about 0900 local time, a pilot and an egg collector were preparing to commence crocodile egg collection activities near King River, Northern Territory, using a Robinson R44 Raven II helicopter, registered VH-IDW and operated by Helibrook. The activity was conducted under a Civil Aviation Safety Authority (CASA) instrument authorising the pilot to carry a sling person (egg collector) on a 100 ft line attached to the helicopter.
At 1024, the crews of 2 other R44 helicopters collecting crocodile eggs nearby became concerned that they had not heard any communications from the crew of VH-IDW, which they reported was unusual. One of those helicopters returned to the area where VH-IDW was last seen and, at 1036, the search pilot found the fatally injured egg collector on the ground, wearing their harness and attached to the sling line, which was disconnected from the helicopter. The helicopter had collided with terrain 44 m beyond the sling person, and the pilot lay beside the helicopter having sustained serious injuries.
The ATSB referred matters concerning possible offences under the Transport Safety Investigation Act 2003 relating to the status of evidence available to the ATSB for the purposes of its 'no-blame' safety investigation to the Australian Federal Police for investigation. The referral did not concern the circumstances of the accident itself. The Australian Federal Police referred the matters to the Northern Territory Police as part of its broader investigations.
What the ATSB found
The ATSB found that the helicopter was likely not refuelled at the en route fuel depot, which was about three quarters of the way between the departure location on the outskirts of Darwin and a clearing near King River where the helicopter and crew were to commence crocodile egg collecting. The pilot did not identify the reducing fuel state before the helicopter’s engine stopped in flight due to fuel exhaustion. During the subsequent autorotation, the pilot released the egg collector above a likely‑survivable height, fatally injuring them. The pilot then completed the autorotation to the ground, but there was insufficient main rotor energy to cushion the landing. This resulted in serious injuries to the pilot and substantial damage to the helicopter.
The ATSB found that Helibrook’s CASA-approved safety management system was not being used to systematically identify and manage operational hazards. As a result, the risks inherent in conducting human sling operations, such as carriage of the egg collector above a survivable fall height, were not adequately addressed.
The ATSB also found that CASA did not have an effective process for assuring an authorisation would be unlikely to adversely affect safety. As a result, CASA delegates did not use the available structured risk management process to:
identify and assess risks
ensure suitable mitigations were included as conditions of the instrument
assess the effects of changes on the overall risk.
This resulted in removal of instrument conditions limiting the height, speed and exposure for the sling person, which permitted carriage of the egg collector at a non‑survivable fall height.
In addition to the above contributing factors to the accident, the ATSB identified the following factors that increased risk but there was insufficient evidence to show they contributed to the accident or severity of the consequences, or to another contributing safety factor. The ATSB identified that CASA's lack of effective process resulted in the continued operation of piston engine helicopters for human sling operations without adequate mitigations. This included the issue of a 3-year instrument to Helibrook shortly prior to the commencement of improved regulations that would require a turbine engine helicopter for human slinging operations. Although conducting the operation with a piston helicopter increased the overall risk of the activity compared with use of a turbine helicopter, previous accident data showed fuel exhaustion was as likely to occur in a piston as it was in a turbine engine helicopter.
Although not likely to result in sudden power loss, engine defects present at the time of the accident likely affected the engine’s maximum power output and fuel consumption. Additionally, Helibrook had likely overrun the helicopter's maintenance, inspection and overhaul periods, which increased the likelihood of the helicopter experiencing a technical failure or malfunction.
The ATSB also found that the pilot’s exposure to cocaine within the previous few days increased the likelihood of fatigue, depression and inattention, however there was insufficient evidence to determine whether these effects occurred.
Finally, the ATSB found that the helicopter's emergency locator transmitter had been removed from its mount prior to the accident. Therefore, it could not activate automatically, which likely delayed the emergency response.
What has been done as a result
CASA implemented significant changes to its internal processes to ensure that the assessment and management of safety risks of new aviation activities (and associated approvals) were standardised in accordance with the CASA Risk Management Manual and that decision-making was appropriately documented. Additionally, CASA developed an ‘exemption protocol suite’ of documents, which detailed the principles, protocols and work instructions for CASA’s regulatory exemption process. CASA also completed and provided exemplar bowtie and aviation safety risk assessments using the structured process.
Following this accident, Helibrook advised that it had ceased operation and the helicopter fleet was being sold. In addition, the chief executive officer/chief pilot was no longer involved with the operation. CASA confirmed that as Helibrook no longer had the required key personnel, it was considered to be suspended from operation. Under those circumstances, the operator’s safety management system was no longer in use.
Safety message
The contributing factors to this fatal accident highlight the significant influence that the actions and decisions of pilots, operators and the regulator can all have on aviation safety.
Fundamentally, this occurrence illustrates the importance of effective fuel management. It is vital to use all available means, including accurate fuel records and quantity cross‑checks, to ensure that pilots accurately know their aircraft’s fuel state. This is especially critical when operating a helicopter where a fuel‑related power loss offers few safe options, such as inside the height-velocity avoid area with a vulnerable human external load. Pilots also should understand the functionality and limitations of any installed low fuel warning systems.
At the operator and regulatory level, effective safety management processes that identify and safely manage hazards are vital to preventing future accidents.
The ATSB referred matters concerning possible offences under the Transport Safety Investigation Act 2003 relating to the status of evidence available to the ATSB for the purposes of its 'no-blame' safety investigation to the Australian Federal Police for investigation. The referral did not concern the circumstances of the accident itself. The Australian Federal Police referred the matters to the Northern Territory Police as part of its broader investigations.
The occurrence
On 28 February 2022, the crews of 3 Robinson R44 helicopters were preparing to conduct crocodile egg collection in Arnhem Land, Northern Territory. Each helicopter was operated by a different aircraft operator, contracted to Wild Harvest Northern Territory, and crewed by a pilot and an egg collector.
One of the helicopters was an R44 Raven II, registered VH-IDW, operated by Helibrook. The method of egg collection included slinging the collector underneath the helicopter, in a harness attached to a 100 ft ‘long line’ (see the section titled R44human external cargo operations).[1]
The pilot of VH-IDW reported that they arrived at Helibrook’s hangar at Noonamah, on the outskirts of Darwin, Northern Territory at about 0530 local time, conducted the daily inspection of the helicopter and found no defects.
The other 2 R44 helicopters involved in the egg collection on the accident day arrived at Noonamah at about 0645. Their crews reported briefing together with the VH-IDW crew. The briefing involved discussing the day’s plan, including who was collecting from which nests, and where they would meet to refuel. The plan was to refuel at Mount Borradaile en route to King River, then collect eggs from about 15 nests located between King River and Maningrida, which was 90 km beyond King River (Figure 1). The crews then planned to refuel at Maningrida, before continuing south-east to collect additional eggs.
At about 0703, the 3 helicopters departed Noonamah for Mount Borradaile, 205 km east-north-east, where fuel drums had been pre-positioned. At 0743, having travelled 111 km from Noonamah, a photo was taken in the cockpit of VH-IDW. The image showed the accident pilot as the passenger, seated in the left front seat, and the egg collector piloting the helicopter from the right seat. Based on the time taken to reach that point, the helicopter probably arrived at Mount Borradaile at about 0816.
Figure 1: Map showing key locations and times
Source: Google Earth with OzRunways data, annotated by the ATSB
The 3 R44 helicopters landed at Mount Borradaile for the planned refuelling, where the crews intended to ‘hot refuel’[2] each helicopter from fuel drums. A witness reported that the 3 R44 helicopters departed Mount Borradaile at about 0830 to track towards King River. One helicopter continued past King River to the north-east and commenced collecting eggs. OzRunways[3] data for the other 2 helicopters, including VH-IDW, recorded their arrival near King River at 0850.
At a clearing near King River, 60 km beyond Mount Borradaile, the second helicopter’s crew retrieved a harness from VH-IDW. Two witnesses reported that the accident pilot was in the left passenger seat and the egg collector was in the pilot seat and flew VH-IDW to King River, where the dual controls were removed. However, the accident pilot and one other egg collector reported that the dual controls had been removed at Mount Borradaile and the pilot had swapped to the pilot seat and flown VH-IDW from Mount Borradaile to King River. While VH-IDW was still on the ground, the second helicopter departed to commence collecting eggs about 12 km to the north-east. Data recorded from an egg collection application showed that the crew of the 2 helicopters, other than VH‑IDW, conducted operations from 9 nests (Figure 2) between 0911 and 1014.
Figure 2: Accident area including King River, accident site and nests
Source: Google earth overlaid with nest collection data, annotated by the ATSB
At 1024, the pilot of one of those helicopters became concerned that they had not heard any radio communications from the crew of VH-IDW since they commenced egg collection operations and were unable to contact them. As a result, the pilot elected to return to the area where they expected VH-IDW to be operating. The pilot travelled in the reverse direction past the 3 planned nests assigned to the crew of VH‑IDW (Figure 12).
At 1036, they located the accident site closest to the first planned nest and landed nearby. They found the sling person (egg collector) fatally injured. VH-IDW was located 44 m beyond the sling person, substantially damaged having collided with trees and terrain (Figure 3). The accident pilot had sustained serious injuries and was found lying beside the helicopter. After providing reassurance to the pilot of VH-IDW, the other pilot returned to their helicopter and briefly became airborne to get mobile reception and call for assistance. The first call to emergency services was received at 1046.
Figure 3: VH-IDW accident site
Source: CareFlight
The second helicopter and remaining crew arrived at the site about 1 hour later. They found spare egg collection equipment from VH-IDW in the clearing where VH-IDW was last seen before the accident. The accident site was between the clearing and the closest of 3 nests that were to be collected by VH-IDW’s crew. No eggs had been collected.
Based on photos and reports from those who attended the site on the accident day, the egg collector’s bucket and pole were the first items in the accident trail (Figure 4). The pole was vertical with one end embedded in the ground. About 4 m beyond the pole, the long line attachment rings were found, also embedded in wet ground, with the long line loosely coiled over about 8 m. The egg collector was found wearing a harness, which was intact, firmly secured and attached to the long line, and their helmet was on the ground nearby. The long line was not connected to the helicopter.
Figure 4: Accident trail
Source: Apple Maps annotated by the ATSB
Following notification of the accident, a CareFlight rescue helicopter departed Darwin at 1122, arrived at the accident site at 1232, and departed with the injured pilot at 1310. As they departed the site, another Helibrook R44 helicopter arrived with Helibrook’s chief pilot, a Wild Harvest Northern Territory representative and an off-duty Northern Territory Police Force officer.
A CareFlight nurse remained at the site until the rescue helicopter returned at 1532 to retrieve the deceased egg collector, departing about 20 minutes later. The crews of the other 3 helicopters reported departing about 20 minutes after the rescue helicopter.
Context
Personnel information
Pilot information
Qualifications and experience
The pilot held a commercial pilot licence (helicopter) with low-level and sling ratings. At the time of the accident, the pilot had recorded about 2,500 hours total aeronautical experience. The pilot’s most recent flight review was on 21 May 2021. The pilot had recorded 340.1 hours of sling experience, the most recent of which was gained in May 2021. The pilot had been contracting to Helibrook for 8–9 years, including for crocodile egg collection. In addition, the pilot operated their own R44 helicopters and contracted to other operators. According to the pilot’s logbook, they had first conducted slinging of human external cargo (HEC) for crocodile egg collection on 13 December 2017. Their last recorded HEC sling time was in March 2020, but the pilot reported having also conducted human slinging for egg collection in the wet season from December to May of 2020–2021 and 2021–2022.
Documents provided by the operator indicated that the pilot had completed a proficiency check flight with the Helibrook chief pilot on 3 August 2021 in the pilot’s R44 II helicopter, which was not fitted with dual hooks. The pilot had recorded a flight time of 0.8 hours in their logbook with no reference to conducting sling operations, whereas the Helibrook Rotary Pilot Competency Check form stated the flight time as 1.1 hours. According to the form, the pilot had demonstrated competency in pre-flight tasks, normal and emergency procedures and the following specialised tasks:
search and rescue
charter
sling operations
croc egg harvesting
aerial advertising – banner towing
supply dropping
surveillance
hover exit entry.
The pilot was also a licenced aircraft maintenance engineer and the head of aircraft airworthiness and maintenance control (HAAMC) for Helibrook.
Medical and toxicology
The pilot held a class 1 aviation medical certificate with no restrictions, valid to 27 May 2022.
A blood sample was taken from the pilot at 1638 on the accident day, 11 minutes after the pilot’s arrival at Royal Darwin Hospital. Toxicology results from the sample identified several substances administered by CareFlight and Royal Darwin Hospital medical staff. Additionally, the results detected 2 metabolites of cocaine – ecgonine methyl ester and benzoylecgonine – at low levels (less than 0.01 mg/L). These results were identified using mass spectrometry and considered to be reliable indications of previous cocaine exposure. These metabolites can be detected in the blood up to 3–4 days after exposure (see the section titled Cocaine metabolites).
Cocaine itself is generally detectable in blood tests for up to 1–2 days after exposure and was not detected in the pilot’s blood.
The pilot had no reported medical conditions and in the self-disclosure section of their aviation medical application, they had advised not using any drugs or recreational substances within the last 5 years. The pilot also advised the ATSB that they did not use cocaine.
Anticonvulsant medication levetiracetam was also identified in the pilot’s toxicology results. There was no evidence of this having been administered by CareFlight or Royal Darwin Hospital medical personnel, although it was consistent with emergency treatment for the pilot's injuries. There was also no evidence obtained to indicate that the pilot had recently visited a doctor, had a condition requiring the medication, or obtained a prescription for it. A pharmacological expert advised the ATSB that even if it had been present before the accident, it was one of the least likely anticonvulsant drugs to interfere with cognitive process as there was evidence of its widespread positive effects on cognition. It was also less likely to produce ataxia[4] and dizziness than other antiepileptic drugs.
Recent history
The pilot reported having limited recollection of events leading up to, and including, the accident sequence. Despite that, the ATSB was able to identify the following activity in the days leading up to the accident.
On 24 February 2022, the pilot was operating a Robinson R22 helicopter (not associated with Helibrook) to locate crocodile nests, when an engine valve failed, requiring the pilot to conduct a forced landing. The pilot reported feeling ‘pretty rattled’ by it.
The next day, after repairs were conducted on the R22, its engine again lost power during take-off. Additionally, the day’s egg collection activities were suspended due to rain and the pilot’s partner reported that they spent a quiet evening at home together.
On 26 February, the pilot was involved in crocodile egg collection activities, which were again suspended due to rain. The pilot consumed alcohol that evening and reportedly attended a party, returning home between 0100 and 0200 the following morning. The pilot left again before their partner awoke between 1000 and 1100 on 27 February. Rideshare records from the pilot’s phone indicated that a car was used between 0243 and 0306, and again at 1040, with no end time recorded.
Information obtained from the pilot’s phone showed that later that day, the pilot started operating VH-IDW at 1545 and conducted crocodile egg collection about 60 km south‑west of Darwin, until 1810. This was consistent with information subsequently provided by the helicopter operator. The pilot’s partner reported that the pilot went to bed at about 2130 that evening and left for work at about 0445 on the accident morning.
The ATSB considered whether the pilot’s activity in the preceding days may have led to them being fatigued at the time of the accident. Specific factors that potentially increased fatigue risk included:
the pilot likely experienced a high level of stress following 2 engine power losses, leading to an unscheduled overnight stay at accommodation away from the pilot’s home
the pilot’s usual sleep pattern was significantly disrupted on one night, getting to sleep around 6 hours after the usual reported sleep time
over the previous 4 nights, the pilot slept in 3 different locations, which had the potential to affect sleep quality
the pilot only had 6–7 hours sleep opportunity on each of the 2 nights before the accident, meaning that the pilot was probably carrying some level of sleep debt at the time of the accident
on the day of the accident the pilot awoke during the window of circadian low, which also has the potential to affect the pilot’s sleep debt
consumption of alcohol or exposure to recreational drugs is known to reduce sleep quality
hot, humid weather conditions, such as those in the Northern Territory in February, are associated with reduced sleep quality and quantity.
While a number of these factors could combine to increase likelihood, there was insufficient evidence to establish if the pilot was likely experiencing a level of fatigue known to affect performance at the time of the accident. In a statement provided to the ATSB in response to the draft report, the pilot reported that they were not tired or affected by alcohol or drugs on commencing the operation of the helicopter.
Egg collector information
At the time of the accident, the egg collector had passed their private pilot licence (helicopter) flight test but not yet been issued that licence.
Wild Harvest Northern Territory (WHNT) held a suite of documents for crocodile egg collection, which included safe work method statements[5] and procedures. WHNT engaged multiple helicopter operators each season to undertake crocodile egg collection. At the start of each egg collection season, those intending to conduct egg collection, including pilots and collectors, attended a WHNT ground-based training and administration day. Both the accident pilot and the egg collector attended this training on 1 December 2021, and had signed safe work method statement sign-on sheets for:
ground operations for croc egg collecting, including:
equipment checks
personal protective equipment
safety around helicopters
firearm safety
selecting and collecting nests
human sling operations (see the section titled Operator risk assessment)
safe handling of fuel.
Aircraft information
General history
VH-IDW was a 4-seat Robinson Helicopter Company (Robinson) R44 Raven II (R44 II) helicopter, certified in accordance with United States (US) Federal Aviation Regulations (FAR) Part 27 and manufactured in the US in 2008. The helicopter was first registered in Australia in July 2008 and had a standard certificate of airworthiness and was to be operated in the normal category.[6] The helicopter was powered by a 6-cylinder Textron Lycoming IO-540-AE1A5 engine derated to 205 brake horsepower (BHP) with a maximum 5-minute take-off power of 245 BHP.
In December 2009, at 62.2 total hours in service, the helicopter was involved in a dynamic rollover that resulted in sudden stoppage/damage to the main/tail rotor and the engine. The aircraft was returned to Robinson for overhaul, including the engine. The hour meter was reset to zero, and the helicopter was returned to service in May 2012.
Helibrook commenced operating VH-IDW on 15 October 2020 and, as the registered operator, was responsible for the continuing airworthiness of the helicopter. VH-IDW was to be maintained in accordance with the airframe and engine manufacturers’ maintenance schedule, which required a periodic inspection every 100 hours or 12 months, whichever occurred sooner. The engine and airframe were subject to overhaul at 2,200 hours or 12 years, whichever occurred first. Additionally, any instructions for continued airworthiness on approved modifications, such as cargo hooks, were to be complied with. The helicopter was fitted with an hour meter activated by a combination of oil pressure and an electrical switch on the collective.[7] The hour meter was an acceptable means of recording time in service, however it could be disconnected, which would prevent flight hours being recorded.
On 22 October 2020, shortly after the helicopter was purchased by Helibrook, a 100‑hourly inspection was carried out on VH-IDW, at which time the helicopter’s total time in service, recorded in the maintenance records was 1,577.9 hours and the hour meter read 1515.75. The maintainer reported that in November 2021, the hour meter was rolled forward 62.2 hours to match the helicopter’s total time in service for ease of record-keeping. At the accident site, the helicopter hour meter read 2,070.05 hours, which equated to 2,007.85 hours since overhaul.
Maintenance release
A maintenance release is required to be carried on an aircraft as an ongoing record of the aircraft’s time-in-service and airworthiness status. Subject to conditions, a maintenance release is valid for a set period, nominally 100 hours in service or 12 months from issue.
A daily inspection was required to be carried out and the maintenance release signed to show the inspection had been completed, prior to the first flight of the day. The inspection and certification could be made by any pilot licenced to fly the aircraft, or an appropriately licenced aircraft maintenance engineer. After the last flight of the day and before the aircraft was next flown, the total daily flight time was required to be entered and the progressive total time in service recorded.
VH-IDW’s maintenance release, current at the time of the accident, was provided to the ATSB on 3 March 2022. It had been issued on 7 February 2022, with 2,036.3 hours total time in service recorded. The accident pilot’s signature was on the maintenance release for 8, 9 and 10 February, with 7.6, 4.3 and 1.5 hours recorded respectively.
The accident pilot’s signature was on the maintenance release for the accident day. The pilot initially reported having conducted the daily inspection of VH-IDW on the morning of the accident, found no defects and signed the maintenance release. However, the pilot subsequently reported being unsure when they had signed the maintenance release for the accident day’s flight.
No defects had been recorded on part 2 of the maintenance release. Additionally, there were no entries on part 2 of the maintenance releases from when the fuel calibration was certified on 1 May 2020 to the accident day to indicate any issue with the fuel calibration, calibration card or fuel quantity indication.
Recent maintenance
On 15 January 2022, due to a pilot reporting that the engine was ‘low on power’, the maintainer adjusted the magneto engine timing and renewed the spark plugs.
On 7 February 2022, the maintenance organisation completed a periodic inspection of VH-IDW. During that inspection, the No. 6 cylinder was replaced due to failed compression, however, there was no documentation supporting that a post-replacement compression check had been conducted. Other maintenance items completed at that time included replacement of the engine-driven fuel pump and the tail rotor assembly.
On 11 February 2022, with 2,050.09 hours recorded in the engine logbook, a Helibrook pilot had reported an ‘intermittent miss in flight’ to the maintainer. The maintainer identified that the left magneto had a failed drive bearing and replaced it with an overhauled magneto. The right magneto timing was also adjusted. The worksheet stated ‘compression test ok’ but no figures were recorded. The maintainer reported checking compression during troubleshooting for the intermittent miss but did not record the figures as they were satisfactory. The maintainer then recorded conducting a post-maintenance flight of 0.8 hours with no issues identified.
Recorded hours and other observations
The pilot’s logbook did not contain any entries relating to the operation of VH-IDW, and the pilot’s last logbook entry was in their own helicopter on 12 February 2022. Additionally, and despite the pilot reporting conducting egg collecting using VH‑IDW in previous seasons, the earlier VH-IDW maintenance releases covering the previous egg collection season did not contain any entries by the accident pilot. However, this did not preclude the pilot having flown VH-IDW after another person conducted the daily inspection and signed the maintenance release.
The pilot reported that VH-IDW had flown significantly more hours than were recorded and that the hour meter was never operating when they flew it, although they could not recall whether the hour meter was operating on the accident morning. The pilot estimated that they had flown VH‑IDW for about 70 hours in the 2021–22 crocodile egg collection season and had also flown it during 2020–21. The ATSB obtained invoices that indicated the pilot had conducted over 36 full days of egg collection in 2020–21 and 2021–22 seasons, all of which were reported to have been in VH‑IDW. Due to the apparent discrepancy in operating hours, the ATSB compared the hours recorded on VH-IDW’s maintenance releases from November 2020 to the accident day with:
the pilot’s time (in units of days/half days) invoiced for crocodile egg collection
spreadsheets recording hours for helicopters (by operator and helicopter type) and day/half‑day rates for personnel involved in crocodile egg collection
the pilot’s phone records of start and stop times for VH-IDW
recorded egg collection data (see the section titled Crocodile nest data)
fuel uplift records
evidence of VH-IDW being operated for a purpose other than egg collecting.
There were 21 days identified when VH-IDW was operating and there was no entry on the maintenance release, some of which were recorded as 10 to 11 hours of helicopter operation. For all other entries for crocodile egg collection, only a portion of the spreadsheet time was recorded – including as little as 10% of the hours recorded on the spreadsheet on single days. On those days, collected nests were recorded on the crocodile egg collection application and for many of them, the pilot had retained a record of VH-IDW start and stop times consistent with the spreadsheet’s recorded hours. The review of the spreadsheets and comparison with VH-IDW’s maintenance release hours included consideration of whether multiple Helibrook R44s were operating on a given day.
The accident pilot reported that the helicopter had not ‘missed a beat this season’, then subsequently described VH-IDW’s performance as good and that it flew well, but that it was nearing the end of its overhaul life and had problems in the weeks prior to the accident. These included a damaged inlet valve, a loose induction tube and fuel injector. The latter 2 items were recorded as rectified on the maintenance release on 14 December 2021. There was no documented recent inlet valve replacement identified but the No. 2 cylinder exhaust valve was replaced on 22 April 2021. When questioned whether there was any indication that the helicopter was overrunning the 100-hour inspection intervals, the maintainer reported that it was difficult to determine whether a helicopter had done 100 or more hours when it arrived for maintenance.
A maintainer who previously maintained Helibrook helicopters from June 2016 to January 2020, reported that they had previously found a Helibrook R44’s hour meter disconnected. In addition, the operator had leased a helicopter from the maintainer and a comparison of recorded GPS flight data with documented flight times showed that the hour meter had been disconnected and about 4 hours of the 14 hours flown during the cross-hire period were not recorded on the maintenance release.
A Civil Aviation Safety Authority (CASA) airworthiness inspector produced a report as part of CASA’s review of this accident. The report identified that VH-IDW’s engine-driven fuel pump had been replaced at reducing hours since new: 733.4 in 2017, 651.9 in January 2020, then, after purchase by Helibrook, at 387.8 hours in April 2021 and 263.2 hours in February 2022. The report stated this was indicative of flight hours not being accurately recorded.
Fuel capacity, calibration and indications
The R44 II POH stated that for tanks fitted with bladders (including VH‑IDW), the main fuel tank capacity was 115 L, of which 112 L was usable, and the auxiliary tank capacity was 65 L, of which 64 L was usable. Of the combined 180 L capacity, the total usable fuel was 176 L. The POH defined usable fuel as the fuel available for flight planning.
Unusable fuel is the amount of fuel in the tank/s below which continued running of the engine while performing the most adverse manoeuvre cannot be assured. Below this level, there is the potential to un-port[8] the fuel tank outlet due to fuel movement. In straight and level flight, some of the unusable fuel is likely to reach the engine. In the R44 II, the main tank to engine fuel union is located on the inboard side of the tank, forward and near its base.
Calibration of the main and auxiliary tank fuel gauges was required every 48 months. The last calibration was conducted by a CASA‑authorised maintainer in May 2020. The calibration is shown in Figure 5. The associated placards for the main and auxiliary tank gauge calibration were affixed in the cockpit, but the auxiliary tank placard was damaged and illegible (Figure 6).
Figure 5: Fuel tank gauge calibration as recorded in May 2020
Source: Supplied
Figure 6: VH-IDW cockpit photo showing fuel gauges and placards
Source: ATSB
The main tank placard stated that the low fuel warning light would illuminate when 20 L total fuel (usable and unusable) remained (Figure 6). According to the maintenance manual, the low fuel warning switch was not subject to calibration. The organisation that conducted the fuel calibration reported that, to establish the 20 L figure, they drained the tank, checked the low fuel light was illuminated, then added fuel until the low fuel light went out. The pilot reported that the light would illuminate with 18 L total fuel remaining. Both those figures differed from the POH, which stated that the low fuel warning light would illuminate with approximately 3 US gallons (11 L) of usable fuel remaining (14 L total fuel in the main tank) (Figure 7).
Figure 7: Low fuel warning
Source: Robinson R44 II Pilot’s Operating Handbook
The Robinson R44 II POH included Safety Notice SN-15 – Fuel exhaustion can be fatal, which advised pilots never to rely solely on the fuel gauge or low fuel warning light but to always record the hour meter reading each time the fuel tanks were filled. This enabled pilots to monitor fuel consumption and endurance. In addition, the POH required the pilot to visually check fuel quantity at each tank during the pre-flight. VH‑IDW was also fitted with a fuel flow transducer and an associated Fuel Scan (totaliser) instrument in the cockpit. The instrument could display fuel flow and other parameters including fuel used and fuel or time remaining. However, the display of accurate fuel quantity relied on the correct amount of fuel to be entered following engine start and the in-flight photograph taken en route from Noonamah for Mount Borradaile identified that the Fuel Scan instrument display was not visible.
Manifold pressure limits
Maximum continuous power manifold pressure limits were prescribed in the POH (Figure 8).
Figure 8: R44 II Maximum continuous power, manifold pressure limits
The red square depicts the limit for the conditions at the time the in-flight photo was taken.
Source: Robinson Helicopter Company, annotated by the ATSB
Flying with a higher manifold pressure than the prescribed limit may exceed the approved torque for the rotor drive system. Robinson advised that if excessive power was held continuously, the helicopter would exceed the normal flight envelope, likely causing stress to drive system components that were not designed for such loads.
Robinson safety notice SN-37 – Exceeding approved limitations can be fatal, stated:
Every second the limitations are exceeded, more stress cycles occur and additional fatigue damage can accumulate within the metal. Eventually, a fatigue crack will begin and grow until a sudden failure occurs…Do not operate the engine above its placarded manifold pressure limits…
Robinson also advised that higher‑than‑normal manifold pressure for a given airspeed could also indicate an engine issue. If one or more cylinders were not operating correctly, higher manifold pressure would be required to produce the same power. In this case, the higher manifold pressure may not exceed the approved torque for the rotor drive system.
Hydraulic flight control assistance
The main rotor flight controls are hydraulically boosted to eliminate cyclic[9] and collective feedback forces. The hydraulic system operates at a pressure between 450–500 psi and consists of a pump, 3 servos, a reservoir, and interconnecting lines. The pump is mounted on, and driven by, the main rotor gearbox. A servo is connected to each of the 3 push-pull tubes that activate the main rotor swashplate. The reservoir is mounted on the steel tube frame behind the main rotor gearbox and includes a filter, pressure relief valve, and pilot-controlled pump bypass valve. A sight gauge for pre-flight fluid level checks is incorporated in the reservoir, which has a vented filler cap.
The pump bypass valve is solenoid-actuated and controlled by the hydraulic switch on the cyclic. When selected to HYD (on), the solenoid is deactivated. This fail-safe ensures hydraulic assist is retained in the event of a loss of electric system power. The switch should be on from start-up to shutdown, except during the hydraulic system check or simulated hydraulic failure training. When selected to off, power is applied to the solenoid and high-pressure hydraulic fluid is returned to the reservoir, removing hydraulic assist from the controls.
Robinson reported being unaware of any instances of the solenoid actuating in flight and causing a loss of hydraulic assist in the controls. The ATSB occurrence database contained 3 hydraulic related occurrences in R44 helicopters since 1997, none of which resulted in a loss of control or an accident. The first was the result of the pilot inadvertently switching off the hydraulic master switch in flight, the second was a failure of the hydraulic pump, and the third was a hydraulic leak.
Inadvertent engine stoppage
Robinson advised that there had been several accidents in which a pilot had inadvertently induced an engine stoppage by rolling off the throttle too fast. This had occurred in flight training when simulating an engine failure and in response to abnormal situations such as rapid engine RPM changes or discrepancy between engine and rotor RPM.
Skids
The helicopter had previously been fitted with floats, which had been removed, but the skid extenders necessary for float fitment remained fitted to the helicopter.
Emergency locator transmitter
The helicopter had a factory mount for an emergency locator transmitter (ELT) and associated wiring in the main rotor gearbox bay however no ELT was fitted to VH‑IDW, nor was one required to be. When fitted, the ELT is connected to an external antenna. The ELT had an arm/on/off switch, and a remote switch was located next to the cyclic, with a default position of ‘armed’.
Pannier
A pannier for the carriage of egg collection equipment was fitted on the left side of VH-IDW. This had been approved by a CASA-authorised aeronautical engineer under an engineering order, although the associated rotorcraft flight manual supplement (RFMS) was not inserted in the POH.
Dual hook system
VH-IDW was originally fitted with dual hooks for HEC under an engineering order. The engineering order required that the hook system be maintained in accordance with the instructions for continued airworthiness and operated in accordance with the associated flight manual supplement. The engineering order was replaced by a CASA-approved supplemental type certificate (STC)[10] in 2021. The system and hook part numbers and the maintenance requirements were unchanged, and the only change was a reduction in the maximum allowable hook weight from 150 to 129 kg (and the associated placard). This was to provide a greater safety margin for HEC operations for the same hook and its strength rating.
The STC approved nominated R44 and R44 II helicopters to be:
modified with a dual Onboard Systems International cargo hook kit for HEC operations in accordance with Master Document List R5106-07-R5 (28 July 2021)
maintained in accordance with Instructions for Continued Airworthiness (ICA) R5106-09-R11 (21 July 2021)
operated in accordance with RFMS R5106-25-R13 (11 June 2021), which was required to be inserted in the POH. The associated RFMS was not contained within VH-IDW’s POH.
The dual hooks could attach to rings on a 100 ft long line, enabling the carriage of a person below the helicopter. The 2 hooks could be released by the pilot by pressing 2 independent buttons of the primary quick release system (PQRS) or pulling 2 manual handles of the back-up quick release system (BQRS). In addition to 2 independent actions, the PQRS buttons were recessed into a housing to further reduce the likelihood of inadvertent pilot activation. The dual hook and release systems were designed to provide redundancy in case of failure.
Following electrical or manual activation, the hook arm would remain open, until it was manually relatched by pushing the hook up by hand to the closed/locked position (Figure 9). (Note: the red component in Figure 9 is the manual release lever).
Figure 9: Onboard Systems hook open and closed/locked (same part number as those installed on VH-IDW)
Source: Onboard Systems
Serviceability
The Onboard Systems HEC dual hook system was installed on VH-IDW on 23 October 2020. The ICA required the external load operation hours to be recorded when the primary hook, or both hooks, were used for external load operations in flight.[11] There was no evidence that external load operation hours were recorded on either hook. There was also no record in the aircraft maintenance documentation of the required 100-hourly/annual checks having been conducted. Finally, one of the hooks had been removed from another helicopter prior to being installed on VH‑IDW and had exceeded its 3 years in‑service limit.
The RFMS included the requirement for the pilot to conduct a functional check of the quick release systems prior to commencing the day’s HEC operations. The pilot reported that their normal procedure was to test that the primary and back-up quick releases were functional before the sling person hooked up but could not recall whether they had done so on the accident day.
Meteorological information
The helicopter departed Noonamah on the accident morning at about 0703. The weather conditions at the time included a light northerly wind and scattered low cloud. At 0743, the helicopter was en route, 60 NM beyond Noonamah and 50 NM from Mount Borradaile. The nearest Bureau of Meteorology weather station was at Point Stuart (Figure 1), where, at 0800, the wind was a north-north-westerly at 10–14 kt, the temperature was 27.5 °C and the QNH[12] 1008 hPa.
The Bureau of Meteorology weather station nearest the accident site was South Goulburn Island Airport (Warruwi), 29 km north-north-west. At 0930, the recorded meteorological conditions were westerly wind at 6 kt, temperature 29 ⁰C, dewpoint 24 ⁰C, QNH 1010 hPa and no cloud. Similar conditions were recorded at Oenpelli, 63 km south-west, and Maningrida, 90 km east-south-east of the accident site.
Recognising that the winds at these recording stations were light and the actual accident time unknown, the accident trail was consistent with it being approximately into wind. At the sea level elevation of the accident site, with QNH 1010 hPa and temperature 29 ⁰C, the calculated pressure altitude was 90 ft and density altitude[13] was 1,770 ft.
Recorded data
Mobile devices
There was a mobile telephone and an iPad on board the helicopter at the time of the accident with the potential to contain data relevant to the accident sequence. The ATSB was able to recover information from the pilot’s phone pertaining to their activities in the days prior to the accident, records of hours the pilot operated VH-IDW and previous maintenance release practices. However, no data directly relevant to the accident flight was able to be recovered.
The egg collector’s phone had been operating in the vicinity of the accident site, but was missing and could not be obtained by the ATSB for analysis and the iPad was severely damaged in the accident impact, rendering any stored data unrecoverable.
Phone records show the last mobile data session before the accident, commenced on the pilot’s phone at 0847:37 and the egg collector’s phone at 0858:16. The egg collector was sent a text message at 0923:44 but the message was not received. This indicated that the phone was either out of mobile range, which occurred below about 300 ft in the vicinity of the accident site, or was off/not powered.
In-flight photo
A georeferenced in-flight photo was taken at 0743 on the accident morning, 111 km beyond Noonamah and 94 km prior to the Mount Borradaile refuelling stop, on a direct track between the 2 locations (Figure 10). The photo showed:
the fuel gauges reading just below three quarters full
the Fuel Scan instrument was not operating
the manifold pressure about 24 inches of mercury (inHg)
an indicated airspeed 90 kt
the engine and rotor RPM about 103%
a chronometer indicating 00:45.
The photo also showed the accident pilot seated in the left seat as a passenger and the egg collector piloting the helicopter from the right seat.
Figure 10: Cut-out of in-flight photo taken at 0743 showing cockpit indications
Source: Northern Territory Police, annotated by the ATSB
As detailed in VH-IDW’s POH, for the pressure altitude at sea level and temperature 30 °C, the maximum continuous power was 23.1 inHg manifold pressure (red box in Figure 8). Based on the aircraft’s height, temperature and QNH at Point Stuart and interpolating the POH table, the maximum continuous power was about 23 inHg. Robinson advised that exceeding the manifold pressure limits with an engine functioning normally would be expected to result in a higher airspeed or rate of climb than depicted in the photo.
Assuming VH-IDW departed Noonamah at 0703, which was the time one of the other R44s departed, it averaged 90 kt ground speed to the in-flight photo location.
Crocodile nest data
A custom-built iPad application named ‘Crocpad’ was used to record the collection of eggs and nest locations. In the week prior to the accident, pilots (including the accident pilot) had conducted flights to locate the nests and entered each nest’s location into Crocpad.
The Crocpad data included fields for the device name, status, created date and modified date. The device name was that used by the person who located the nest (for example, ‘my iPad’). The created date contained the date and time the nest was located, at which time the nest’s status was set to LOCATED. When a nest was subsequently either COLLECTED or DELETED, the modified date was amended with the date and time this occurred. This did not need to be the same person or Crocpad that located the nest. The device name was not updated when a nest was collected or deleted, and remained as the device name that had been used to locate the nest. The Crocpad data would update to the server when in mobile range, which the accident site was not. The iPad that was running Crocpad in VH-IDW had not updated the server with any information before it was severely damaged in the accident impact. The 9 nests amended on 28 February are shown in Table 1 and Figure 11.
Table 1: Crocpad data for 28 February 2022
Nest number
Local time
Status
1
0911
COLLECTED
2
0912
DELETED
3
0915
COLLECTED
4
0935
COLLECTED
5
0955
COLLECTED
6
0955
COLLECTED
7
1009
COLLECTED
8
1011
COLLECTED
9
1014
COLLECTED
Figure 11: Crocpad data showing nests recorded as collected or deleted on 28 February 2022
Source: Crocpad data overlaid on Google Earth, annotated by ATSB
On the accident morning, after departing the King River set-down area, the pilots and egg collectors of the 2 helicopters other than VH-IDW, reported meeting at a patch of 3 nests (No.1 to No. 3), then one helicopter went to a single nest (No. 4), before re-joining the crew of the other helicopter at another patch of nests (No. 5 to No. 9).
The accident pilot reported that one of the nests in the vicinity of the accident site could be collected on foot (without slinging). It was not known whether the crew of VH-IDW visited that nest before slinging towards the target nest where the accident occurred. However, the first person to attend the accident site reported no eggs had been collected and there was no indication any of the nests in the area had been visited.
Figure 12: Inset from Figure 11 showing nests in the vicinity of the accident site with the status of ‘located’ on the Crocpad data
Source: Crocpad data overlaid on Google Earth, annotated by ATSB
OzRunways data
OzRunways flight path data was obtained for 2 of the R44 helicopters, including VH-IDW. The data contained tracks commencing about halfway between Mount Borradaile and the King River, and ceasing near the clearing where VH-IDW and its crew were last seen prior to the accident (Figure 13). The data for VH-IDW was recorded on the egg collector’s iPhone from 0841:28 to 0850:13 local time and uploaded to the OzRunways server. The data covered about 15 NM, equating to a ground speed of about 100 kt. The other track was from 0840:22 to 0850:15, indicating the 2 helicopters were operating in company.
Figure 13: Recorded OzRunways tracks of VH-IDW and another R44 helicopter
Source: OzRunways data overlaid on Google Earth, annotated by ATSB
No OzRunways data was retrieved from the accident pilot’s phone and no data had uploaded to the server from the pilot’s phone or iPad. The pilot reported that they generally used landmarks to navigate for the ferry flight, and would only use OzRunways, in combination with Crocpad, for the egg collection.
Communications
The egg collector carried a UHF radio to enable communication with the pilot. It was reported that as the egg collector usually held a bucket in one hand and a pole in the other, it was difficult for them to press the transmit button to talk to the pilot, so they would usually use hand signals to communicate. The accident pilot subsequently reported that egg collectors could easily hold the crate and pole in one hand, making the radio accessible. Additionally, the accident pilot reported that as the helicopter radio was selected to VHF at the time of the accident, they could not have quickly communicated with the egg collector as it would have required switching the radio selector to UHF.
The pilot who was first on the accident site estimated that the accident occurred at about 0922 while they were on the ground and out of radio range. This estimation was based on the pilot not hearing an unintelligible radio transmission, later attributed to IDW, that was reported to have been heard by the crew of the other R44 which was airborne at the time.
Accident site assessment
The ATSB attended the accident site on 2 March 2022. The site was in a paperbark swamp approximately 440 m east of the clearing where spare equipment was found and where VH-IDW was last seen. From the egg collector to the helicopter, the accident trail lay in an approximately north‑westerly direction towards, and about 150 m before, a nest that was assigned to the crew of VH-IDW.
Assuming a direct transit from the clearing towards the first nest, the trees between where the helicopter probably took off, and where the egg collector was released, were 12–15 m tall. The trees in the vicinity of the target crocodile nest were at least 18 m tall. The bucket and pole were reported to have been found on the ground between trees about 4 m prior to the long line attachment rings. The egg collector was located about 8 m beyond the attachment rings and between 2 trees (Figure 14). On the first tree in the direction of flight, a section of bark had peeled away, about 4–5 m above the ground. While this may have been evidence of possible recent impact, no associated bark was found on the equipment or egg collector.
Figure 14: Accident trail
Source: Northern Territory Police annotated by ATSB
The helicopter impacted the ground upright 44 m beyond the sling person, with the fuselage oriented on a heading of about 060° (Figure 15). The main rotor blades had struck one tall slender tree 3 times, indicating a vertical descent through the tree. The tree was about 9 m tall, with 2 distinctive upper branches that forked from the main trunk about 5 m above the ground. One rotor blade severed one upper branch 8 m above the ground, where the branch diameter was 35–40 mm). A blade then severed the trunk at the fork, 5 m above the ground, where the branch diameter was 50–55 mm. The final cut of the main trunk occurred 1.1 m above the ground, which was below the normal main rotor blade height above the ground in a level attitude.
The severed main tree stump (diameter 150 mm) was 2.4 m in front of the helicopter’s nose, leaning about 55° in the direction of main rotor rotation. The helicopter was facing over 90° right of the apparent direction of travel, consistent with rotation of the fuselage due to the main rotor blade’s impact with the tree trunk or pilot pedal input. During the accident sequence, one main rotor blade fractured about 1 m inboard from the blade tip, with the fragment located 45–50 m north‑west of the wreckage. It was noted that the main rotor pitch control link associated with this blade had fractured in overstress, with no damage to the other pitch link.
Figure 15: Site overview, with the orange arrow showing approximate direction of the accident trail
Source: Northern Territory Police, annotated by the ATSB
In addition to multiple rotor strikes to a single tree, indications of a mostly vertical descent, slightly right and nose-down attitude and a heavy impact included:
the landing gear had splayed almost to horizontal, and fractured
the forward cross tube was pushed up into the cabin, significantly reducing the available space in the rear cabin, resulting in empty egg crates in the middle of the back seats being distorted and wedged up against the internal cabin roof
both skids had fractured forward of the front struts
deformation to the nose was more pronounced to the right of the landing lights
the pilot’s seat was collapsed towards the front right corner.
The base of the pilot’s seat had crushed, as designed, to absorb impact forces. The pilot’s restraint had reportedly been cut by those first on site and used in providing first aid to stabilise their injuries.
All the helicopter components were located in the vicinity of the accident site, indicating that there was no in-flight breakup. The forward doors were not installed, and the rear doors had been ejected on impact but were reportedly moved and placed under the pilot for support.
The helicopter was in a black dirt swamp and surrounded by water, up to about 0.5 m deep. The swamp had a gentle flow away from the helicopter, in a northerly direction, toward a nearby creek that was part of the King River system. When the ATSB attended the site 2 days after the accident, both fuel tank caps were correctly fitted, there was no fuel smell, no fuel in the auxiliary tank and a very small quantity of fuel at the bottom of the main tank.
The impact forced the right side of the transmission deck up to contact the underside of the auxiliary tank, such that the fuel drain could not be accessed. There was no evidence of fuel leaks on the transmission deck, from either tank or associated fuel lines. The right-side low orientation of the helicopter would have directed any fuel in the main tank to the engine fuel hose union near the base of the inboard side of the tank. Any fluid that leaked from the helicopter would have flowed downstream and away from the site.
The first person to arrive at the site could not recall checking the fuel tanks, but 2 others who arrived in the second Helibrook helicopter reported having observed the first person to arrive look in one tank and advise that there was fuel visible. In addition, the Helibrook chief pilot who was on board the second Helibrook helicopter reported looking in one tank and seeing a shimmer of fluid however, they did not dip the tanks to check the quantity. The first person to arrive at the accident site reported that there had been a fuel smell, but subsequently reported that the fuel smell may have been from a damaged jerry can that had been behind the pilot’s seat at the time of the accident.
A CareFlight first responder who arrived at 1232 reported that there was no smell or indication of fuel, only hydraulic fluid, which created a sheen on the water. A photo taken at 1555 on the accident day showed a slick on the water near the accident site. It was unknown whether that was from hydraulic fluid, fuel or another source. The ATSB obtained images of the site taken in June 2022, 4 months after the accident, in which there was no evidence of vegetation dieback that can indicate fuel contamination. However, 206.2 mm of rainfall had been recorded at the nearest Bureau of Meteorology weather station (Warruwi Airport) since the accident, reducing the likelihood that vegetation dieback would be evident.
The first person to arrive at the accident site also reported that there was no power to the aircraft when they arrived, but they switched off the electrical system master and alternator switches as a precaution, and rotated the main rotor blades to provide shade for the pilot. They further reported the fuel mixture control was in the full rich position and the magnetos were selected to ‘Both’, consistent with positions identified by the ATSB on site. The engine RPM governor switch, located at the forward end of the collective, was found in the OFF position. The hour meter read 2070.05. The stowage space under both forward seats was inspected, with nothing being located under the left seat and several small items, including a damaged headset, under the pilot’s seat. The POH and maintenance release were not in the helicopter.
No oil was found in the hydraulic system, however, hydraulic fluid was observed on the main transmission deck. The hydraulic switch was selected ON at the cyclic. Flight control continuity from the tail rotor to the main rotor head, above the transmission deck, was established. The fuses for the belt tensioning actuator, in-use and spare, were noted to be the correct amperage and undamaged. All 4 drive belts were present. The distorted pannier prevented easy access to the left side of the engine and the underside of the helicopter was not accessible due to the collapsed landing gear and distortion to the engine cowls. On-site images indicated that the engine was probably above the water level, however, water may have entered the cowls on impact.
The tail cone remained connected to the fuselage. There was no damage to the upper vertical fin and horizontal stabiliser. The tail cone and the lower vertical fin displayed compression damage consistent with terrain impact.
The tail rotor assembly was secure and rotated freely. Oil was evident in the tail rotor gearbox sight glass and the chip detector was clear of metal contamination. The tail rotor blades were in new condition and undamaged, with some light wood debris at the tip on the leading edge of one tail rotor blade. There was some corresponding minor scuffing to a partially submerged, sodden tree branch immediately under the tail rotor, consistent with contact following a vertical descent.
The ELT’s mount was located in the main rotor gearbox bay however, the ELT was not installed. The ELT harness, which included a quick disconnect socket, and antenna cable, were secured with cable-ties. The ELT end of the antenna cable was secured to the helicopter frame with tape. The remote switch, located next to the cyclic, was in the default ‘armed’ position.
Following on-site examination, VH-IDW was slung from the site by another helicopter. People on the ground when VH-IDW was lifted from the accident site did not report observing any fuel leaking from the helicopter. During the retrieval, VH-IDW was lifted multiple times, and also put down heavily en route to Jabiru, Northern Territory due to a technical issue with the slinging helicopter. At Jabiru, VH-IDW was loaded upright onto a truck and transported 252 km by road to a secure facility in Darwin for detailed examination. The switch positions identified on site were not altered during the retrieval and arrived in the same positions.
Helicopter examination
Hook system
The hook electric and manual release systems could not be functionally tested due to impact damage. However, both manual release T handles were found in the down position (not activated) and visual inspection did not identify any faults with the dual hook system. The hooks were found in the ‘up and locked’ position when the wreckage was lifted during retrieval from the accident site. Following activation, the hook arm would normally remain open, until manually relatched by pushing the hook up to the closed/locked position. In this instance, having had to open to release the egg collector, they were likely closed by the subsequent helicopter ground impact.
Drivetrain
Continuity of the drivetrain was established from the main rotor gearbox to the tail rotor gearbox, including all flex couplings. There was some distortion to the main rotor gearbox input driveshaft yoke and flex coupling, along with minor scraping on the transmission deck under the intermediate flex plate which was consistent with an unpowered rotor system (see the section titled Autorotation) during a heavy impact.
The main rotor gearbox could be rotated without restriction and the oil level was in the middle of the sight glass. Several main rotor gearbox mounts were fractured and the chip detector was damaged from perforating the transmission deck but was clear of debris. There was no indication of overheating of the main gearbox or clutch assemblies.
The clutch assembly was disassembled with no obvious damage to the sprags or race surface, consistent with the helicopter being in autorotation during multiple tree strikes before impacting the ground.
The belt tensioning actuator assembly had fractured in overstress at the connection to the upper bearing assembly and at the actuating rod. The actuator rod extension was consistent with properly engaged belts, which included assessment of expected stretch typical of their time in service. The drive belts were intact and appeared in reasonable condition although they were displaced from their respective sheave grooves, which was typical of heavy impact and actuating rod failure.
Main rotor
The main rotor head droop stops were undamaged with no evidence of excessive teeter or mast bumping. Both blades exhibited rearward distortion about mid-span, with some mild upward coning, indicative of low energy during the descent and tree strikes (Figure 16). The fractured pitch link failed in overstress at the upper rod end thread. The corresponding rod end was secured to the pitch horn, with a slight inboard deflection consistent with the rotor strike and blade fracture. The associated fractured blade had more pronounced coning near the hub, and impact marks and deformation on the lower surface, consistent with the blade being able to rotate about the pitch axis (up) following the pitch link failure. The blade tip was likely liberated at the stump strike.
Figure 16: VH-IDW’s main rotor blades showing rearward bending and fracture
Both main rotor blades were cut at the accident site to facilitate transport to Darwin
Source: ATSB
Control continuity
Flight control continuity was established throughout. Many control tubes had fractured due to overstress associated with impact, but the corresponding rod ends were secured to bell cranks. The left seat quick-disconnect (dual) controls were not installed and the cyclic boot was in place. The collective friction device had fractured due to impact forces. There was some movement in the collective, but it was restricted due to damaged control tubes. The overtravel spring was bent in a manner consistent with impact damage.
Engine RPM governor
A power source was applied to the governor motor. The motor operated in both directions with no evidence of interference. The governor wiring loom connector was secure and there was no evidence of loose or deformed pins. The governor switch was functional, with the governor itself sent to Robinson for testing under supervision of the US National Transportation Safety Board and found serviceable.
Hydraulics
The aft servo return line tee union was found to have fractured in overstress. The filter was clear with no sediment and the pump was secure. The solenoid that actuated the pressure shut-off valve was also tested and found functional.
Emergency locator transmitter
As detailed above, on-site examination identified that no ELT was fitted to the helicopter. The ATSB was subsequently provided with an ELT by the helicopter operator, who reported that they had removed it from the site after the accident. They advised that it was typically carried under one of the seats, otherwise it would get wet and erroneously activate. The produced ELT was registered to a former Helibrook chief pilot and not associated with any aircraft registration. It appeared intact, in reasonable condition, was switched off and its battery was due to expire in August 2022.
The Australian Maritime Safety Authority confirmed that previous unintended ELT activations had occurred due to water ingress and identified one record of activation of the ELT associated with VH-IDW, which occurred on 28 December 2021. A company representative for VH-IDW had advised the authority that the ELT had self-activated, likely due to water making contact with the ELT while collecting crocodile eggs. That ELT was not the one provided to the ATSB.
Warning and caution lights
All warning and caution lights were inspected, and electrical continuity confirmed. The filaments of the low rotor, low fuel, alternator and governor warning lamps were subsequently inspected under a microscope with none found stretched or broken as sometimes occurs if illuminated at impact. However, due to variables that affect the rate of acceleration applied to the filament, the absence of filament stretch does not enable a conclusion regarding whether or not the light was illuminated.
Electrical system
The helicopter battery was found out of the battery box but still connected to the helicopter by the battery leads. The alternator control unit was secure and connected.
Hour meter
One of the 2 electrical connections at the back of the hour (Hobbs) meter was found finger tight. Despite that, the connector would not move freely and had a lock washer under the nut to prevent it from coming loose during operation. However, only a small amount of hand pressure was needed to move the connection, consistent with it having been tightened by hand rather than with a spanner or socket.
Indications of engine rotation at impact
There were no indications of engine rotation at impact, evidenced by:
no rotational damage to the engine cooling fan or housing
no slippage to the cooling fan retention nut alignment mark
no evidence of rotational scoring to the alternator housing or cooling fan and backing plate.
Significantly, impact damage and bending to the upper sheave forward end, lower surface was consistent with impact with the starter ring gear, and showed defined teeth impact marks, with no smearing (Figure 17).
This strongly supported the ring gear being stationary (engine stopped) when the helicopter collided with terrain.
Figure 17: Upper sheave damage from impact with non-rotating starter ring gear
Source: ATSB
Powerplant
External engine examination
External examination found no evidence of a catastrophic engine failure. The throttle butterfly was fully open at the fuel control unit, however as the impact forces would have tended to pull it open, the throttle position prior to impact could not be determined.
Oil
The engine oil cap and dipstick were secure, and the sump plug was relatively clean. The ATSB drained 8.6 L of oil from the engine with no significant debris found in the oil. The recommended maximum engine oil quantity was 9 quarts (8.5 L). Although the oil level slightly exceeded the maximum recommended capacity, it would not have affected the engine’s performance. The oil filter was opened and inspected with nil contamination identified on the filter element.
Air
Induction air enters through an opening on the right side of the fuselage and passes through the air filter within the air box. Air then passes along a flexible sceet duct, through the fuel control unit and into the engine. The air intake was damaged consistent with accident impact, but there was no evidence of blockage or ingestion of foreign material. The air box casing was distorted, also consistent with accident damage, though the filter was clean and there was no sign of blockage. The induction sceet hose had been crushed consistent with impact forces. The induction hose was also checked for delamination, due to a previously-identified issue with some induction hoses, and none was evident.
Engine examination
The engine was shipped to a CASA-authorised maintenance facility for examination under ATSB’s supervision. Differential compression checks were carried out on the assembled engine. Cylinders No. 3 and No. 6 were below the limit of 60/80, which the engine manufacturer advised was the point that removal and overhaul should be considered (Table 2). However, cylinder compression is normally checked on a warm engine, as a cold engine may not provide reliable results.
Table 2: Compression checks of assembled engine – red denotes below limit
Cylinder No.:
1
2
3
4
5
6
Compression
78/80
70/80
45/80
60/80
78/80
0/80
The cylinders were then removed from the engine and subjected to a second, differential compression check on a test bench. During testing, the valves were tapped to ensure any debris was not preventing a good seal. All cylinders then reached or exceeded 70/80 except cylinder No. 6, which only attained 5/80. The leak from cylinder No. 6 was visually identified as coming from both valve seats.
The valves from cylinder No. 6 were removed and the seating surface contact was examined. The seating faces were uneven (nonconcentric), particularly on the intake, and the exhaust seat had a low spot consistent with the valve not sealing properly (Figure 18). The poorly seated valves would have accounted for the low compression although the valves appeared in good condition with no evidence of carbon build-up. The No. 6 cylinder had been overhauled in 2016 and a vacuum pressure test was reportedly conducted at the time to check for leaking, however the results weren’t recorded. After overhaul, the cylinder was stored until installation in VH-IDW in 2022.
Figure 18: No. 6 cylinder intake and exhaust seats showing nonconcentric valve seating and low spot
Source: ATSB
The engine examination also found corrosion in all intake tubes, consistent with post-accident moisture from the impact in the swamp.
Prior to removing the cylinders, the valve trains were removed, and the hydraulic plungers were returned to a dry/deflated condition. After reassembly, the rocker arm to valve clearances were checked and only 5 of the 12 clearances were found to be within the engine manufacturer’s service limits. Table 3 shows the resulting clearances, with those out of service limits highlighted in red. Valve clearances were set on installation of the cylinder and can vary with wear. Insufficient clearance may prevent the valve from closing properly and excessive clearance can reduce valve lift and duration.
Table 3: Rocker arm to valve clearance – red denotes outside limits (0.28–0.80”)
Cylinder No.
Intake valve
Exhaust valve
1
0.110
0.047
2
0.022
0.024
3
0.032
0.036
4
0.016
0.095
5
0.000
0.052
6
0.000
0.047
The low compression in cylinder No. 6 would reduce the maximum power output and at any achievable power output, the fuel consumption would be higher than an engine with compressions within service limits. No defects were identified that should have resulted in sudden power loss or engine stoppage.
The ATSB also obtained an expert opinion from the engine manufacturer, regarding the engine and specifically the low compression result. They advised that low compression in the cold test scenario was not necessarily representative of results obtained from a warm engine. They also stated that the low compression would not result in a significant power reduction or sudden engine stoppage.
Loose B nut
At the engine examination, it was identified that the ‘B’ nut[14] on the fuel control unit (FCU) was loose – about 1.5 turns from tight. This was not indicative of its security at the time of the accident as it was loosened by an ATSB investigator during engine removal prior to shipping for examination.
Ignition system
The engine data plate recorded the engine-to-magneto timing as 20° before top dead centre. The left magneto[15] timing to the engine was found at about 35° and the right magneto timing at 23°. The incorrect timing of the left magneto was assessed as having resulted from impact forces, which resulted in mount fracture and anticlockwise rotation of the magneto that advanced the timing. The external oil filter impacted the right magneto.
Testing of spark plugs and visual inspection of the ignition leads found no defects of the ignition system.
The magnetos were functionally tested and internally inspected at a CASA-authorised electrical and instrument maintenance facility, under the supervision of the ATSB. The magnetos were run on a test bench and both functioned throughout the normal operating range, with nil faults. The magnetos were then partially disassembled for internal examination and testing including points gap and continuity, internal timing, coil and capacitor serviceability. Both magnetos were found to be in normal operating condition.
Fuel system examination
Fuel tanks
The fuel system includes one main and one auxiliary tank, a gascolator, and a shut-off valve, with the associated pilot control knob located between the front seats. The fuel shut-off selector knob was found separated from the control tube and free to rotate however, the valve position was consistent with the fuel selected to the on position. The auxiliary tank was correctly interconnected with the main tank and, due to it being mounted higher than the main tank, would empty first while fuel remained in the main tank. The inter-tank flexible hose assembly was found clear of obstructions.
The fuel tank bladders remained intact despite splitting along riveted joins and punctures to the outer aluminium tanks. The aluminium tanks showed impact damage and subtle deformation (Figure 19 and Figure 20). Robinson assessed that the deformation of the fuel tanks was consistent with ‘lower fuel quantity’ but could not determine whether the deformation was due to impact damage, bulging of internal contents, or a combination of both. Robinson provided an image of an auxiliary tank that was known to have been nearly full at impact for comparison, which presented severe bulging over the entire tank (Figure 20). When compared with the exemplar image, the damage to VH-IDW’s fuel tanks was assessed as representative of the high vertical impact resulting in severe distortion to the airframe around the tanks, with little or no fuel within. This was also consistent with an ATSB investigation into a previous Robinson R22 accident, in which the tank was half-full on impact and displayed distinctive bulging from the internal contents that was not evident in the deformation of VH-IDW’s tanks.
Figure 19: VH-IDW’s auxiliary and main tanks showing subtle deformation and compression damage
Source: ATSB
Figure 20: An exemplar auxiliary tank known to be nearly full at impact and VH-IDW’s
Source: RHC, annotated by the ATSB
All remnant fuel was drained from the main tank on arrival at Darwin. It comprised about 250 ml of blue fuel (Figure 25), contained minimal debris/sediment and was tested clear of water. No fuel was found in the auxiliary tank. Noting as detailed previously (see the section titled Fuel capacity, calibration and indications) that the helicopter’s fuel system had 4 L of unusable fuel, the relatively small recovered quantity indicated that fuel had either been removed from the tanks after the accident or, considered more likely, had leaked out following the accident and/or during the transport from the accident site to Darwin.
Pressurised fuel system
The pressurised fuel system includes an engine-driven fuel pump, an electric (auxiliary) fuel pump and a fuel return line, which allows pump supply in excess of engine demand to return to the fuel tanks. If pressure from the electric pump is low in flight, a pressure switch illuminates the auxiliary fuel pump caution light. Return fuel passed through the fuel pressure relief valve (FPRV) and then flowed to a tee junction connected to the auxiliary tank. The return fuel jet and tee assembly were found to be installed correctly.
The FPRV was tested on a rig, to simulate both fuel return and static leak from the tank back into the engine fuel system. The FPRV fully opened at about the expected parameter however, a small bypass at lower pressures was noted. Robinson reported that the flow curve was similar to other FPRVs they have seen with significant time in service, and advised that:
We have done extensive testing, with [US Federal Aviation Administration] FAA involvement, on valves with variations in their flow curves, and found that they have very little to no effect on engine operation, both with and without the electric (auxiliary) pump operating and not operating. We found that the only FPRV valve condition that had any effect on the engine operation was a valve that was simulated as being stuck in an excessively open position, and in that case the stuck valve resulted in illumination of the auxiliary fuel pump caution light in idle and run-up (as well as at flight power levels).
The electric fuel pump was connected to a power source and operated. The pump was then disassembled, and the pump vane could be rotated manually. The electric motor was worn, with brushes almost down to the leads and the commutator grooved (Figure 21).
Figure 21: Electric fuel pump showing worn brush and commutator
Source: ATSB
There was no sign of particulate contamination or water in the fuel system.
The mechanical (engine-driven) fuel pump serial number matched that recorded as being installed on 7 February 2022. The pump was not blocked, and no defects were found. In addition, function of the driving plunger was observed with engine rotation.
Fuel control unit examination
The FCU was examined by a specialist at a CASA-authorised maintenance facility, overseen by the ATSB. There was no fuel found in the FCU, and the finger filter was clear. The throttle arm was distorted and there was damage to the FCU body, near the mixture control lever, consistent with impact forces. The nozzles were all visually clear and were bench tested. The fuel flow was within the service limits for overhauled nozzles (31.4–32.6 lb/h) except No. 6, which was slightly low (31.0 lb/h). The fuel system specialist advised the slightly reduced flow would not stop the engine from operating.
On the test bench, the FCU tested slightly high (running slightly rich) at the lower power setting, and within limits at all other settings including maximum power. The specialist advised that it was not uncommon for the low-test point to become overly rich. During the testing, flushed fuel was passed through a filter membrane with no contaminants collected. The FCU diaphragm was in good condition and there was no evidence of water contamination in the FCU. Throughout the examination and disassembly no seals or O-rings were found to be failed or damaged. The throttle mechanism was functional.
Fuel system disruption
The fuel lines, flow divider and gascolator were all clean, and empty of fuel. The gascolator drain valve was found depressed against the firewall when examined at the Darwin hangar but reset when manipulated. Upward forces during impact distorted the aircraft structure around the drain assembly resulting in the drain extender tube, used to compress the drain valve, bending and splitting (Figure 22).
Following removal from the accident site, yellow sand was observed in the end of the tube, which was consistent with the site where the helicopter was set down during the wreckage retrieval. The sand likely entered the tube as the skids were removed prior to extrication of the wreckage from the swamp, leaving the tube as the lowest point below the fuselage. The gascolator bowl was dry and the filter screen was clear. Examination of the cowls did not identify any discolouration or staining that would be associated with leaking fuel, either prior to, or after the accident.
Figure 22: Gascolator, drain valve and tube, and R44 II Illustrated Parts Catalog extract
Source: Robinson Helicopter Company and ATSB
The fuel flow transducer, positioned between the fuel control unit and flow divider, had a fractured outlet fitting. The fracture surface was consistent with impact damage, with no evidence of pre‑existing fatigue. On behalf of the ATSB, Robinson conducted a test by removing the fuel line (and transducer) from the FCU outlet with the fuel valve open, mixture full rich and throttle full open. Robinson found that due to gravity, the fuel flowed out at a significant rate and would eventually empty the tanks. Loose black organic soil consistent with the accident site filled the transducer end of the fractured fitting (Figure 23), which likely would have been dislodged at the fuel flow rate demonstrated by Robinson.
The flow divider was opened and noted to be dry and clean, and there were no contaminants or restrictions that would have prevented fuel flowing through each of the nozzles and into the cylinders.
Figure 23: Fractured fitting between transducer and flow divider
Source: ATSB
Fuel system indications
The fuel gauges and low fuel switch were independent systems, in that the low fuel switch would illuminate the low fuel warning lamp, independently of the fuel sender position. The float-operated low fuel switch assembly, located in the main tank, was electrically tested, while manipulating the float up and down, and found to be functional. Additionally, the low fuel switch and lamp were signed off as having been tested by the maintainer on 7 February 2022, as part of the periodic inspection.
The ATSB removed the fuel quantity senders from both tanks and tested the sender calibration in Darwin in June 2022. Further testing of the main tank senders and gauge was conducted by Northern Territory Police on behalf of ATSB in August 2023.
Both senders moved smoothly throughout the operating range. The R44 Maintenance Manual fuel quantity sender check specified positioning the float arm at 4 noted heights and measuring the resistance at each point to verify it was within the specified tolerance. The main tank sender could not be positioned to the up stop height and at the down stop was slightly below the down stop height for the testing, and measured slightly above the resistance range at the intermediate heights. When the fuel gauge was connected to the sender and a power source, the fuel quantity indicator needle moved smoothly from empty to full. The 4 sender test heights corresponded to the gauge indications at Empty, 1/4,1/2 and Full. As a result of the sender float arm position, the gauge very slightly overread (within a needle-width) at the lower 3 indications.
The results were sent to Robinson for expert assessment. Robinson advised that the testing indicated the main tank gauge would have been reading slightly higher than what was actually in the main tank, but ‘nowhere near’ the calibration sticker figures, which indicated the main tank gauge was underreading.
Examination of the auxiliary tank sender base plate identified a slight bend to the sender pole and that the strainer and siphon assemblies were distorted. It could not be determined if the distortion was associated with the fuselage impact forces, or pre-existing. Regardless, the strainer distortion would not have affected fuel flow to the tank interconnect hose. In addition, the siphon, part of the fuel tank drain system would have no effect on fuel supply to the engine. The ATSB determined that the auxiliary tank sender was within the required resistance range at the up and down stops.
Partial power loss
Robinson advised that main rotor blade strike, or strikes, to a tree could stall an engine at low power or idle, prior to impact with the terrain. The ATSB assessed all available evidence against the engine manufacturer’s troubleshooting tables for Low power and uneven running and Failure of engine to develop full power. In addition, the 29 items on Robinson’s troubleshooting checklist for low power were reviewed. All applicable items were tested where possible, within the constraints of damage. Nothing was identified that would likely result in a sudden onset of low power.
Fuel considerations
Fuel uplift
Procedure for filling tanks
The placard adjacent to the auxiliary fuel tank stated that the procedure to fill the tanks to full fuel entailed filling the main tank, then the auxiliary tank, then topping up the main tank. This procedure was required due to the self-levelling of the interconnected tanks.
The Helibrook operations manual included a procedure for hot refuelling (with the engine running). The manual stated that Robinson helicopters were not to be refuelled with the engine running,
unless a person remained at the controls and an authorised person who has undertaken training recorded on the Aircraft Refuelling Training Record Form 16 is available to carry out the refuel.
The Helibrook safety manager advised that they did not have a completed form for the pilot or the egg collector of VH-IDW, and there was no other evidence to indicate whether they had undertaken the training. The egg collector in the second helicopter to land at Mount Borradaile previously flew and collected eggs for Helibrook and was the only person present who had completed the required training to hot refuel a Helibrook R44 helicopter.
Noonamah
Based on interviews with the helicopter operator, pilot and fuel supplier, and the 2 most recently delivered fuel batch receipts, the Noonamah fuel storage tank contained blue 100 low lead (LL) Avgas. A total fuel quantity of 440 L was recorded as being taken from the Noonamah tank on 28 February, but there were no records of the quantity uplifted to individual helicopters. As well as VH-IDW, at least one of the other 2 R44 helicopters was reportedly refuelled when they arrived at Noonamah at about 0645 and several jerry cans were also filled from the Noonamah storage tank. The Helibrook R44 helicopter that flew to the site after the accident may also have used fuel included in that total.
The quantity and source of fuel remaining in VH-IDW prior to refuelling on the accident morning could not be determined. The accident pilot reported that they would have filled the helicopter to full at Noonamah, in accordance with normal procedures. They also stated that their usual practice was to set the chronometer to zero after fuelling the helicopter. Other pilots reported that normal practice was to ensure sufficient fuel to get to Mount Borradaile, but not necessarily to fill both tanks.
In a submission provided to the ATSB following review of the draft report, one of the egg collectors operating on the accident day reported that VH-IDW was filled with 100 LL fuel at a Helibrook base near Sweets Lagoon, 33 NM from Noonamah at the end of the previous day’s activities. They further reported that they were present at the hangar on the accident morning and had not observed VH-IDW being fuelled. Based on that account, if the helicopter was not refuelled at the hangar on the accident morning it would have departed Noonamah with 23-25 L less than the full fuel tank capacity.
Mount Borradaile
As detailed previously, based on the georeferenced in-flight photograph, VH-IDW probably arrived at Mount Borradaile at about 0816. This time was consistent with the departure and arrival time recorded on a GPS device on the third R44 helicopter to arrive at Mount Borradaile that morning.
There were no records of the fuel uplifted at Mount Borradaile. Those present at Mount Borradaile reported that the R44 helicopters were hot refuelled. The accident pilot reported that their normal action was to always fill the helicopter to full at Mount Borradaile.
An Airbus/Eurocopter AS350 helicopter, with a pilot and crewman onboard, had landed at Mount Borradaile before the three R44 helicopters arrived. The helicopter was associated with the crocodile egg collection and its pilot was waiting for the pilot of the third R44 helicopter, who was the operator of the AS350, to assist with a maintenance issue with the AS350.
In preparation for the R44 refuelling, the AS350 crewman rolled 2 200 L drums out, checked they were marked WHNT, and verified they were labelled 100/130 green Avgas. They further recalled that the first drum had been partly used, and its lid was on tightly and difficult to open.
The helicopter crews reported that VH-IDW arrived first of the 3 R44s at Mount Borradaile. There were consistent recollections that the egg collector was in the pilot seat of VH‑IDW, and the accident pilot was in the passenger seat of VH-IDW, when it arrived. Pilot 2 (P2) and egg collector 2 (E2) were in the second helicopter and pilot 3 (P3) and egg collector 3 (E3) in the third.
When P3 arrived, they reportedly went immediately to the AS350 and did not witness the refuelling. The accident pilot could not confidently recall the refuelling events at Mount Borradaile, other than that they got into the third R44 and moved it up to the fuel drum. P2 reported that there was no drum pump carried in VH-IDW that day, and the pump used for refuelling was from the second helicopter. P2 and E2 reported that the pump from their helicopter was used by the accident pilot to put fuel into the main tank of VH-IDW, before the second helicopter moved to the drum. A submission to the ATSB following review of the draft report included a statement made in April 2023 by E2. In their statement, E2 reported that they had not seen VH-IDW being refuelled at Mount Borradaile.
In a statement to the ATSB in March 2022, E3 reported that when they arrived in the third helicopter at Mount Borradaile, they went to hold the hose for the accident pilot, who was getting ready to fuel VH‑IDW. They recalled that the third helicopter was refuelled next, and the second helicopter was still refuelling when the other 2 helicopters departed Mount Borradaile. However, in a subsequent statement in September 2022, E3 stated that they observed the egg collector partially fuelling VH-IDW before they took over and personally filled VH-IDW to full after first helping to refuel the third helicopter.
The AS350 crew reported that the 3 R44 helicopters left Mount Borradaile at 0830, which was consistent with the OzRunways recorded data for 2 of the 3 helicopters.
Based on the planned fuel figures, each R44 would have consumed about 80–90 L of fuel to reach Mount Borradaile. They therefore needed at least 80–90 L to fully fill at Mount Borradaile (noting that would have resulted in a minimum of 50% of the fuel in the tanks being 100/130 Avgas). The pump transferred about 1 L per revolution from the drum to the tank. After refuelling, the standard operating procedure required pilots to conduct fuel drains from 3 points on each helicopter to check for water and other contaminants. It was possible to fill each helicopter within a few minutes, particularly as several people capable of pumping fuel and conducting fuel drains were at Mount Borradaile.
The WHNT fuel drums at Mount Borradaile contained green-coloured 100/130 ‘leaded’ fuel.[16] The same person who rolled out the 2 fuel drums for the R44 pilots to refuel on the accident day, subsequently identified those drums and provided samples to the ATSB for testing. The person identified that as the drums had been reused, they had old 100 LL labels on the side, and the current 100/130 fuel labels on the top (Figure 24). WHNT was also clearly painted on the drums. The person checked the labels and seals, and recalled that the fuel in the drums was green.
Figure 24: WHNT fuel drum at Mount Borradaile showing distinct paint and labels. Inset: Fuel sample
Source: Supplied, annotated by the ATSB
The first drum rolled out was emptied on the accident morning then placed upside down by the AS350 crewman. As a result, when that crew person subsequently obtained fuel samples on behalf of the ATSB, the drum was distinctive as it had mud on the lid from having stood inverted. It was identified as the drum most likely to have been used first on the accident morning and VH‑IDW was reportedly the first helicopter to land at Mount Borradaile that morning. Samples from all 4 WHNT 100/130 drums at Mount Borradaile were taken to Darwin by WHNT and the ATSB arranged for the fuel to be tested.
The ATSB was subsequently advised that there were many empty fuel drums at Mount Borradaile, including some containing 100 LL located near the 100/130 drums. This raised the possibility that the drums used on the day of the accident may have been misidentified when samples were subsequently collected on behalf of the ATSB. However, a photo of one of those drums showed it was not painted with WHNT but was labelled with a different crocodile farm name and had a fuel expiry date of 13 October 2021. Additionally, the owner of the fuel supply reported that due to the remoteness and the criticality of having fuel available, they would not expect pilots to use fuel purchased for other operators and had not been advised of any fuel being wrongly taken.
Fuel testing and analysis
Testing of the fuel drained from VH-IDW found it was consistent with 100 LL fuel, partially evaporated due to handling post-accident (see Appendix A – Fuel analysis). Gas chromatography with mass spectrometry testing of the VH-IDW sample found that it comprised less than approximately 1% 100/130 Avgas (1% was the testing limit of distinguishing between 100 LL and 100/130). There was also no evidence of contamination with Jet A-1, diesel, premium 98 petrol (car fuel) or Opal (low-aromatic car fuel used in the Northern Territory).
Samples from the 4 drums at Mount Borradaile containing green 100/130 fuel supplied by WHNT were obtained. The fuel from the 2 drums identified as having been used on the accident morning, were tested and found to meet the specifications of 100/130 fuel in accordance with the supplied batch test results. Figure 25 shows the colour of the Mount Borradaile sample compared with the remaining fuel recovered from VH‑IDW.
Figure 25: Comparison of Mount Borradaile sample and VH-IDW fuel
Source: ATSB
Fuel jerry cans
Images provided to the ATSB from first responders at the accident site showed 2 jerry cans in VH‑IDW, one behind each of the front seats. The jerry cans were subsequently removed from the helicopter and were not at the site when the ATSB arrived, nor subsequently provided to verify their contents. Those first on site and the accident pilot reported that both were full at the time of the accident and had probably been filled at Noonamah that morning. The jerry can behind the pilot seat was reportedly damaged on impact and may have leaked fuel, although no one reported detecting fuel leaking at the time.
The ATSB considered the potential effect of interference with the site in relation to the laboratory fuel testing results. The only plausible scenario that permitted both the described full refuelling at Mount Borradaile with 100/130 fuel and the residual 100 LL identified in testing was if 40 L of 100 LL fuel was poured from the jerry cans into VH-IDW after the accident and then most of it subsequently leaked away before the ATSB assessed the tank fuel quantity on arrival at the accident site. To dilute the 100/130 fuel component to less than the tested 1%, there would have to have been less than approximately 800 ml of fuel remaining in tank at the time prior to the addition of 100 LL from the jerry cans, comprised of approximately 50% 100/130 and 50% 100 LL fuel.
No one at the site, including the first to arrive, who was there until 1555, reported seeing anyone pour fuel into, or drain fuel from, VH-IDW. It was also reported that fuel from the 2 jerry cans was emptied into other helicopters that attended the site prior to their return to Darwin. Further, the empty jerry cans were then reportedly used to transfer fuel from a fuel drum to a helicopter at Mount Borradaile on the return to Darwin.
Fuel flow
The Helibrook operations manual required pilots to use a fuel flow rate of 60 L/h for flight planning purposes for R44 II helicopters for ‘normal, specialised and holding’, and a fixed reserve of 20 minutes (20 L). In a submission to the ATSB draft report, the pilot stated that VH‑IDW’s normal fuel burn was 60 L/h. The operator reported that VH-IDW normally consumed about 65–70 L/h.
Robinson does not publish fuel flow rates for their helicopters. They provide a planning fuel flow of 60 L/h and guidance including to record the hour meter reading each time fuel tanks are filled, check the fuel level in the tanks visually, continually check hour meter and fuel gauges, and to refuel before the main tank fuel gauge reads less than 1/4 full.
With 176 L of usable fuel (full fuel) with no reserves, VH-IDW would have the following endurance:
2 hours 56 minutes at 60 L/h
2 hours 42 minutes at 65 L/h
2 hours 31 minutes at 70 L/h.
Required engine power, and therefore fuel flow, is highest during take-off, landing and while hovering. As such, when conducting low‑speed flight while carrying an external load, the engine would be operating at high power and fuel flow rate.
Low compression in one cylinder results in less power produced compared to the other cylinders. Therefore, a higher power setting and increased overall fuel usage would be required to achieve the same airspeed as a fully serviceable engine. The actual increase in fuel consumption on the accident day due to low compression in the number 6 cylinder could not be quantified as the specific compression was unknown.
Regarding in-flight fuel re-planning and quantity measurement, the Helibrook operations manual stated:
Single-pilot low-level aerial work activities undertaken by this company are such that the priority of maintaining control of the aircraft and awareness of their surroundings prevents more than a visual scan of the fuel quantity gauges. For these operations where the recording of fuel figures may be detrimental to safe flight, fuel state will be managed using visual gauge checks, watches and reference to elapsed flight time.
The pilot reported never using the fitted fuel flow meter and the display was not visible in the in‑flight photo.
Operational information
Loading and performance
The RFMS required that the weight and centre of gravity be checked to verify the helicopter remained within the approved limits throughout each flight. Although not required to be documented, there was no evidence that a weight and balance assessment had been conducted on the accident day.
Based on photos, interviews, and evidence from the accident site, when the helicopter departed Noonamah on the accident morning with the pilot and egg collector on board, its contents included:
slinging equipment
6 to 10 egg collecting buckets and poles
2 x 20 L jerry cans filled with 100 LL Avgas fuel
8 x 1 quart (0.95 L) engine oil cartons
fishing rod/s, firearms, drink bottles, ammunition and personal effects.
The ATSB did not have access to many of these items and it is unknown if other items may have been on board but removed from the site. Therefore, the helicopter’s exact total weight at the time of the accident could not be calculated. However, based on the available information, the helicopter was likely operating below the maximum allowable weight of 1,134 kg at the time of the accident.
In addition to the gross weight limit, it was also a requirement of the RFMS for HEC operations that the aircraft was operated at a weight at which the helicopter could hover out of ground (OGE) effect[17] at least 3,000 ft above the ground. Due to the above uncertainty associated with the helicopter’s actual weight (including its fuel quantity), and the identified low engine cylinder compression, it was not possible to determine whether OGE performance existed at the time of the accident. However, in the ambient conditions at the time of the accident, the helicopter would not have met the 3,000 ft out of ground effect hover capability requirement at its maximum gross weight (1,134 kg).
The RFMS also stated that the maximum weight permitted on the dual hooks was 129 kg including the sling person, line, harness, equipment, bucket and crocodile eggs. At the time of the accident, the egg collector with equipment weighed 118 kg and the line weighed 26 kg. The total weight on the hooks was therefore 144 kg plus the bucket, pole and small items that were not weighed. Although this exceeded the permitted weight, there was no evidence the hooks or associated equipment had failed.
Autorotation
In the event of an engine power loss, drive is no longer supplied to the rotor system and the pilot must lower the collective and sometimes conduct an initial flare to maintain sufficient rotor RPM while establishing autorotation. In an autorotation, the rotor blades are driven solely by the upward flow of air through the main rotor. The total energy available for an autorotation in the event of a power loss comes from the kinetic energy of the rotor blades and airspeed, and potential energy, which is directly proportional to the height.
Several factors affect the rate of descent in autorotation: bank angle, density altitude, gross weight, rotor RPM, trim condition, and airspeed. Two aspects pilots commonly use for managing distance travelled and rate of descent, are airspeed and rotor RPM.
In an autorotation in an R44 II, the rate of descent is high at zero airspeed, lowest at 55 kt, and increases again at higher airspeeds. The only energy available to arrest the descent rate for landing is the forward speed of the helicopter and the rotational kinetic energy stored in the rotor blades. Maintaining adequate rotor RPM is essential to ensure sufficient energy to flare the helicopter for landing. The flare is a critical manoeuvre that ensures safe completion of a power-off landing. The flare simultaneously decreases forward speed and rate of descent while increasing rotor RPM. Flaring too far away from the ground will leave the helicopter without sufficient energy to cushion the landing.
The R44 II POH stipulated that in the event of complete power loss, the pilot was to immediately lower the collective to enter autorotation. The specific procedure for power failure between 8 and 500 ft above ground level was:
Lower collective immediately to maintain rotor RPM.
Adjust collective to keep RPM between 97 and 108% or apply full down collective if light weight prevents attaining above 97%.
Maintain airspeed until ground is approached, then begin cyclic flare to reduce rate of descent and forward speed.
At about 8 feet AGL, apply forward cyclic to level ship and raise collective just before touchdown to cushion landing. Touch down in level attitude and nose straight ahead.
The minimum rate of descent during an autorotation was about 1,350 ft per minute at an airspeed of 55 kt and rotor RPM 97% when below 500 ft.
Height-velocity diagram
A height-velocity (H/V) diagram is required for single-engine helicopters certified under FAR Part 27. The diagram:
defines an envelope of airspeed and height above the ground from which a safe power-off or one engine inoperative (OEI) landing cannot be made (FAA, 2014).
The Robinson R44 II Pilot’s Operating Handbook (POH)[18] included the H/V diagram for R44 II helicopters, including VH-IDW (Figure 26).
Figure 26: Robinson R44 II height-velocity diagram
Source: Robinson Helicopter Company R44 II POH
When operating at low speed in the shaded (or ‘avoid’) area on the left side of the diagram, in the event of a power loss, a pilot may have insufficient height to accelerate to the speed required to autorotate successfully (autorotation speed).[19] Above a certain height above the ground, at least 400 ft for the R44 II depending on the density altitude, it is possible for a pilot to achieve autorotation speed even from a high hover (FAA, 2019). In the shaded area on the lower right side of the diagram, the combination of faster airspeed and proximity to the ground provides limited reaction time for the pilot in the event of in-flight emergencies. The FAA Helicopter Flying Handbook (FAA, 2019), stated:
the shaded areas should be avoided, as the pilot may be unable to complete an autorotation landing without damage.
The unshaded region of the diagram shows the combinations of airspeed and height above the ground that allows a pilot to successfully complete a landing in a full autorotation without requiring exceptional skill. At low heights (below about 10 ft) with low airspeed, such as a hover taxi, the helicopter is in a safe part of the H/V diagram. There, a pilot can use the kinetic energy from the rotor disc to cushion the landing with collective, converting rotational inertia to lift. An increase in height without a corresponding increase in airspeed puts the helicopter above a survivable un‑cushioned impact height, until a height is reached from which rotor inertia and gravitational potential energy can be converted to sufficient lift to reduce the vertical velocity at impact to a survivable value (FAA, 2019).
Rotorcraft flight manual supplement
Limitations and procedures for HEC operations
A requirement of certification of the dual hooks for HEC was to have the appropriate limitations and procedures for conducting human external cargo operations incorporated in the rotorcraft flight manual supplement (RFMS). The first draft of the RFMS associated with the STC for the hooks system was developed in 2013, and revision 13 of the R44 RFMS for HEC Dual Hook was approved by CASA, along with the STC, in July 2021.
The CASA-approved rotorcraft flight manual supplement
The CASA-approved RFMS and associated STC were specifically for the activity of collecting crocodile eggs, and some operational procedures were included in the RFMS. The RFMS Introduction stated that it was only valid if the operator also had ‘CASA approved operational procedures for use of the HEC Dual Hook system’.
The RFMS Section 1 General, contained a warning of elevated risk to aircrew ‘and particularly the Human External Cargo (HEC)’ involved in helicopter crocodile egg collection operations. The elevated risks included:
a. Any failure in the attachment of the line to the helicopter, lines and harness, including accidental release actuation, inevitably results in injury or death of the HEC.
b. In any malfunction of the helicopter resulting in an emergency landing, the HEC does not have the protection of the airframe structure and restraint harness.
c. The helicopter is operating most of the time in the corner of the speed/height diagram for which a safe landing may not be possible.
d. Operating the aircraft to safely position the HEC in relation to the ground and obstacles is a high skill, high workload operation.
It then detailed additional risks including the:
‘use of a low powered single piston engine helicopter’
lack of a ‘spotter’ in the aircraft due to R44 weight restrictions
isolated nature of crocodile egg collection
potential for crocodile attack.
Section 2 Limitations included:
a maximum airspeed of 60 kt during HEC operations
maximum 15 kt wind
no operations within 5 NM of lightning
a weight limit such that the helicopter has out-of-ground-effect hover capability at least 3,000 ft above ground level
maximum 129 kg down weight: combined weight carried on the hooks including the HEC person, line, harness, equipment, crocodile eggs and their container
HEC line length between 48 and 105 ft (15–32 m).
The RFMS Section 3 Emergency procedures stated:
Survivability of HEC personnel during an in-flight emergency is best accomplished by having suspended personnel remain attached to the aircraft as it makes an emergency landing. Apart from exceptional circumstances, release of the HEC line is not an operational consideration while human external cargo (HEC) is attached beneath the aircraft. In case of an aircraft emergency, the pilot will normally conduct a landing with HEC attached to the short-haul line. The only exception is the HEC or line snagging on terrain, or the probability that this may happen. The choice by the HEC person to cut away from the line is a personal decision depending on the circumstances and best chance for survival.
WARNING
Short-haul operations are inherently dangerous and could be fatal. This must be discussed in detail during training, re-currency and mission pre-flight briefings.
NOTE
It is imperative that potential emergency scenarios, actions and reactions likely required of all involved personnel are discussed as thoroughly as possible prior to flight.
PQRS [PRIMARY QUICK RELEASE SYSTEM] OPERATION
Emergency use of the PQRS is restricted to circumstances where the pilot judges that the consequences for the HEC person are outweighed by the reduction in risk for the aircraft and aircrew.
…
ENGINE POWER LOSS
In addition to the procedures defined in the [Rotorcraft Flight Manual] RFM
1. Roll away, upwind if possible, away from the HEC person.
2. Attempt to touch down level and clear of the HEC person. If insufficient clearance from HEC person, touch down banked so the rotor will be away from the HEC person.
NOTE
HEC person is to rapidly unhook or cut the lines and lay prone on ground to minimize injury risk from the helicopter.
GRADUAL ENGINE POWER LOSS
1. If obstacles permit, place the HEC person on the ground if possible.
2. Attempt to touch down level and clear of the HEC person. If insufficient clearance from HEC person, touch down banked so the rotor will be away from the HEC person.
NOTE
HEC person is to rapidly unhook or cut the lines and lay prone on ground to minimize injury risk from the helicopter.
In establishing the emergency procedures, the design engineer advised that considerations of the line disconnecting (uncommanded) resulting in release of the HEC, were addressed by the hooks’ compliance with FAR certification standards for hooks for HEC. They reported that it was recognised that engine failure was the biggest risk. In managing this risk, the expectation was that an engine would rarely stop suddenly – usually running rough and degrading over a period of 30–60 seconds before stopping. It was considered that expected behaviour should give a pilot time to manoeuvre the helicopter away from the HEC, preferably downwind.
Furthermore, the design engineer advised that the emergency procedures were based on minimising risk to the HEC because the sling person was unprotected, whereas the pilot had a seat, restraint, and airframe as protection. Jettisoning the HEC from higher than 10 to 15 ft above ground would likely result in fatality, therefore keeping the HEC on the line while the helicopter autorotated, was assessed as offering a better overall outcome. The design engineer reported that at the time of the STC approval, the FAA advised that they could see ‘almost no circumstances in which the pilot would release the HEC’, but that more recently FAA’s emphasis had changed to requiring a very high degree of engine and systems reliability.
Comparison emergency procedures
US Department of the Interior
The US Department of the Interior (DOI) defined the transport of one or more people suspended beneath a helicopter as ‘short-haul’. The DOI Helicopter Short-Haul Handbook outlined minimum policies, procedures, qualifications, training requirements and equipment for helicopter short-haul programs, and was accepted as ‘best-practice’ guidance material.
Preplanning for emergency procedures is a critical component of risk management. Accordingly, each short-haul program must evaluate and discuss potential scenarios and actions that may best mitigate any associated hazards. Training for effective crew resource management should be a part of this process.
It is imperative that everyone involved in short-haul understand how instantaneously an in-flight emergency may occur. Survival of short-haul personnel during an in-flight emergency is best accomplished by having suspended personnel remain attached to the rope while the pilot attempts emergency landing. Examples of formalized emergency planning procedures are outlined below.
WARNING: Short-haul operations are inherently dangerous and could be fatal. This must be discussed in detail during training and recurrency. Release of the short-haul line is a possible consideration while human external cargo (HEC) is attached beneath the aircraft. In case of an aircraft emergency, the pilot may attempt to land with HEC attached to the short-haul line. The decision of any short-hauler to cut away from the line is a personal choice depending on the circumstances and best chance for survival.
The only difference between this text and the CASA-approved RFMS Emergency procedures, was that the DOI Handbook stated that ‘Release of the short-haul line is a possible consideration’, whereas the RFMS stated ‘Apart from in exceptional circumstances, release of the HEC line is not an operational consideration’, while HEC is attached beneath the aircraft. Both documents stated that the HEC survival was best assured by the sling person remaining attached to the line in the event of an emergency landing.
Other dual hooks for HEC RFMS
There were no STCs for dual hooks for HEC for R44 helicopters in Canada or the US. The ATSB reviewed the RFMS and STCs for dual hooks for HEC (using single turbine engine helicopters) that were approved in Canada and the US. Those STCs were used for multiple activities, unlike the R44 dual hooks with HEC for crocodile egg collection, which were only approved for that activity.
In Canada, single turbine engine HEC was only approved for rescue and similar activities considered to be in the public interest, that is, where there is a value of life consideration. The RFMS approved by Transport Canada incorporated only emergency procedures as they related to failure of the hook system. For example, a Transport Canada-approved RFMS for Bell 206L‑series helicopters HEC dual hook system Emergency/malfunction procedures section consisted of:
the need to release both hooks to jettison HEC
actions in the event of (hydraulic) failure of the PQRS to open the HEC hook
uncommanded release of either hook system.
An FAA-approved RFMS for Bell 206L/407 had emergency procedures for the event of electrical failure of the hooks, plus the following statement:
Engine Failure
The presence of an external load may further complicate a failed engine condition. In an emergency, land the rotorcraft as soon as practical.
An FAA-approved RFMS for MD Helicopters MD 369 Emergency procedures stated:
If any aircraft emergency occurs during flight with HEC, the operations should be terminated by landing HEC in the nearest safe area. If during an emergency the aircraft must be landed immediately due to engine failure, or catastrophic control failure, HEC may need to be jettisoned.
1. Land HEC safely to the ground as soon as possible.
2. Release empty long line as required…
3. Refer to basic flight manual Emergency and Malfunction Procedures.
In summary, a Transport Canada-approved test pilot advised that an RFMS associated with an STC for dual hooks for HEC would document how to release a load, and procedures in the event of failure of the hooks or quick release system (QRS), but would not address particular operational scenarios. The expectation was that these would generally be contained in an operator’s standard operating procedures approved by the Operational Authority.
Operator information
Helibrook
Helibrook held an air operator’s certificate issued 2 April 2020, with an expiry date of 31 July 2022. Under the certificate, Helibrook was permitted to conduct charter and aerial work operations, including sling load operations. At the time of the accident, Helibrook had one Bell 206L and 3 Robinson R44 II helicopters.
The 3 key positions at Helibrook were the head of aircraft airworthiness and maintenance control (HAAMC), who was the accident pilot of VH-IDW, the chief executive officer (CEO), who was also the chief pilot, and the safety manager.
Head of aircraft airworthiness and maintenance control
The accident pilot was a licenced aircraft maintenance engineer and had held the role of Helibrook’s HAAMC since 12 July 2019. The Helibrook operations manual defined the HAAMC role as follows.
The safety of aircraft airworthiness and maintenance of aircraft is delegated to the HAAMC. The responsibilities and duties of the HAAMC include, but are not limited to ensuring that appropriate arrangements are made for:
1. Maintenance scheduling
2. Monitoring and recording of aircraft hours, cycles and other information relevant to Maintenance scheduling
3. Monitoring and scheduling of maintenance due and deferred maintenance actions (including deferred defects)
4. The review of Airworthiness Directives for applicability and compliance
5. Defect rectification and unscheduled maintenance
6. Investigation and reporting of defects.
The HAAMC is accepted by CASA under a letter of acceptance and is responsible for ensuring that the aircraft operated are airworthy and maintained in accordance with CASA regulations and directions and liaise directly with the maintenance provider – ultimate responsibility remains with the registered operator.
Chief pilot
The chief pilot was responsible to CASA for all operational matters affecting the safety of flying operations. The chief pilot’s responsibilities listed in Helibrook’s operations manual included:
safe and efficient operation of the aircraft
monitoring operational standards
maintaining training records and supervising the training and checking of pilots and crew including of equipment used
ensuring pilot flight and duty times were accurately recorded
ensuring the aircraft were appropriately maintained.
Prior to holding the chief pilot role, the Helibrook CEO had been subject to CASA enforcement action. As a result, CASA imposed a variation on the pilot’s helicopter licence. The variation required the CEO to attend aviation theory remedial training and testing, and complete four 6‑monthly flight reviews with a CASA-approved examiner. These were aimed at ensuring ongoing proficiency in making appropriate safety judgements.
The CEO reported completing the first of those flight reviews and aviation theory training on 6 July 2019. On the same day, the CEO submitted an application to CASA for approval to become Helibrook’s chief pilot. The applicant’s previous breaches meant they did not meet one of the criteria for the chief pilot appointment, which required the person to have ‘maintained a satisfactory record in the conduct or management of flying operations’. CASA offered the applicant the opportunity to demonstrate an acceptable means of compliance with that requirement and submit a safety case stating how they would manage the risks.
Having provided a response to CASA, the chief pilot applicant was required to conduct 2 flights with a CASA flight operations inspector and complete associated ground activities. The CEO conducted the first CASA assessment flight on 6 August 2019 and was assessed satisfactory. The activities assessed were a charter flight and simulated crocodile egg collection. The examiner identified some gaps in knowledge of recent legislation, which the applicant was reported to be working to address. The examiner’s notes described an experienced pilot with a good safety focus.
The CEO’s second chief pilot assessment flight and ground activity was conducted on 25 November 2019. The examiner commented that the CEO demonstrated the ability to supervise and mentor other pilots and was assessed as suitable for consideration for appointment as chief pilot of Helibrook.
CASA subsequently approved the CEO as Helibrook’s chief pilot on 20 January 2020. Additionally, the CEO was provided with an exemption removing the requirement for the previously imposed 6-monthly flight review checks. As part of the process for the CEO to conduct the chief pilot role, Helibrook introduced a safety management system (SMS) and appointed a safety manager.
Safety manager
The safety manager was recruited by the Helibrook CEO in August 2019. The safety manager was also assigned the roles of operations manager and drug and alcohol management plan (DAMP) officer for Helibrook. Apart from a short period in 2020, when the safety manager worked for Helibrook in the Northern Territory, including as a helicopter charter pilot, the safety manager lived interstate and conducted the safety manager, operations manager, and DAMP officer roles remotely.
Documented key responsibilities of the safety manager included:
maintaining the safety management system and ensuring it was relevant to the operations
conducting hazard and risk identification
conducting incident and accident investigations.
Safety management system
Overview
Attributes of a safe organisation include a healthy safety culture with appropriate risk management processes, which achieves safety objectives through internal responsibility rather than relying on regulatory compliance (CASA, 2019). The International Civil Aviation Organization (ICAO, 2018) defined an SMS as:
A systematic approach to managing safety, including the necessary organizational structures, accountability, responsibilities, policies and procedures.
It is designed to continuously improve safety performance through the identification of hazards, collection and analysis of safety data and safety information, and continuous assessment of safety risks. An SMS seeks to proactively mitigate safety risks before they result in aviation accidents and incidents.
The Helibrook SMS manual version 1.0 was issued on 1 August 2019 and accepted by CASA on 22 November 2019. Although not generally required by CASA regulations at the time, it was introduced to demonstrate a commitment to safety and thereby aid in obtaining CASA’s approval of the chief pilot. The SMS manual outlined the company’s safety policy, objectives, and responsibilities for supporting the SMS and reporting of incidents, risks and hazards. It stated:
HELIBROOK will identify hazards and safety risks to minimise risk to innocent people, clients, contractors, employees, other airspace users and aircraft. It will also maintain the health of all stakeholders, and continually improve safety; these goals will be accomplished through a Safety Management System (SMS).
Helibrook’s SMS manual stated that it was to be updated annually, by the CEO in collaboration with the safety manager, and that safety meetings were to occur monthly and involve the safety manager, CEO/chief pilot and HAAMC.
Safety risk management
Safety risk management includes hazard identification, and safety risk assessment, mitigation and risk acceptance (ICAO, 2018). The safety risk management process is continuous and risk mitigation strategies must be monitored to determine whether they are effective. Helibrook’s SMS manual stated the aim of risk management was ‘to treat or control risks to as low as reasonably practicable’. Their stated risk management tools included a documented risk assessment, evaluation and treatment process, a master risk register, and a regular hazard and risk review process.
Hazard identification
According to ICAO (2018), a hazard can be considered as a dormant potential for harm, which is present in one form or another within the system or its environment. Therefore, hazard identification is the first step in the safety risk management process. The intention is to proactively identify hazards before they lead to accidents, incidents, or other safety‑related occurrences. Hazard identification may also consider hazards that are generated outside of the organisation and outside their direct control, such as weather (ICAO, 2018).
The Helibrook SMS manual listed several means of identifying hazards including reporting systems, audits, staff input, and experience.
Helibrook hazards
The Helibrook hazard register, titled Hazards and Risks, listed items under 7 headings: organisation, operational, helicopter, pilot and flight crew, operating environment, weather and egg collecting. The following 2 lists are relevant to this investigation:
Helicopter:
(a) Preflight checklist
(b) Safety equipment – EPIRB, helmets, life jackets, satellite phone and flares
(c) Equipment lists, equipment and checks
(d) Fuel
(e) Inspection – MRs
(f) Maintenance and status
(g) Inspection and status
(h) Time to rebuild/overhaul
(i) Communications – headsets/radio
(j) Weight/centre of gravity
(k) Fuel margins and range limits
(l) Sling Equipment / Harness equipment PPE
Egg collecting:
(a) Crocodile activity
(b) Terrain
(c) Weather
(d) Pilot and crew performance
On 30 September 2019, in response to a request from CASA, the safety manager identified 13 hazards ‘that have the potential to cause harm to pilots and passengers’ and proposed actions to mitigate associated risks. None were associated with crocodile egg collection operations.
Risk assessment
A risk assessment is a process where hazards and the chances of an adverse event happening due to the hazard were identified, analysed, and evaluated (CASA, 2021). This evaluation was expressed in terms of likelihood and consequence and should highlight the risks to be considered before and while carrying out an operation.
Organisations should have multiple layers of controls or defences in place to manage their identified hazards (CASA, 2014). Risk assessments should be carried out across all levels of an organisation and at different stages in the operation. These could consist of a formal, documented process or a continuous ongoing mental assessment carried out by a pilot, or a combination of both. An example of a formal risk assessment would be an operational risk assessment conducted by the operator to consider and evaluate the risks associated with the type of work being undertaken.
The Helibrook operations manual stated that the ability to identify hazards and assess risks was an important component of their continuous safety improvement process. It stated that if a risk assessment was required, the chief pilot would conduct and document the process, which included assessing the risk, developing risk control strategies and implementing them, then assessing those controls. The Helibrook operations manual standard operating procedure for crocodile egg harvesting included that in the event of an aircraft failure:
the sling person must have a clear understanding of the risk and implications of such an emergency
the risk of injury will be reduced providing all height and speed limitations are adhered to
prior to slinging, the pilot must advise the sling person of the high risk nature of the operation and what steps shall be taken to reduce the risk.
Risk register
Safety risk management activities should be documented, including any assumptions underlying the probability and severity assessment, decisions made, and risk controls implemented (ICAO, 2018). A tool such as a risk register could be used to ensure identified hazards were tracked and mitigated as part of a formal risk management process of prioritisation, documentation, and assessment. The register could include the hazard, potential consequences, assessment of the associated risks, and any controls put in place to manage the risk (ICAO, 2018).
Safety reporting system
The effectiveness of a safety reporting system partly relies on the promotion of a positive reporting culture and proactive identification of safety deficiencies. One way of achieving this is by clearly stating that reported information will be used solely to support the enhancement of safety (International Civil Aviation Organization, 2018). This also included a culture where people can report without fear of punishment (Reason, 1998). The Helibrook SMS described a formal reporting system as a key element of the SMS.
Safety culture
CASA SMS booklet 2 – Safety policy and objectives stated that good safety management ‘is not about having an SMS manual on the shelf…it needs context to be effective’. Further, that the ‘ultimate responsibility for safety rests on the shoulders of senior managers’, who should demonstrate a commitment to safety. This included maintaining a positive safety culture.
Safety culture has been defined as 'the set of enduring values, behaviors and attitudes regarding safety, shared by every member at every level of an organization' (SM ICG, 2019). More simply, it is ‘what goes on when no-one is watching’ (EASA, n.d.). Additionally, the effectiveness of a safety management system has been shown to be dependent on the safety culture (SM ICG, 2019).
The Hudson Ladder defined 5 steps, or maturity levels, in the evolution of safety culture (Figure 27). The first step – pathological (‘who cares as long as we’re not caught’) – was not really a culture of safety (Hudson, n.d.). The second step, a reactive safety culture, was one in which safety was a burden imposed by the regulator. In a reactive culture, action was only taken in response to an incident, and often involved blame or punishment. In a poor safety culture, ‘not everyone takes safety seriously, are not watchful, are complacent and compromise too readily’ (ARPANSA, n.d.). In contrast, a positive safety culture ensures operations are conducted as safely as practicable, which reduces the risk of accidents occurring.
CASA described safety culture elements, in which an example ‘enabler’ of a positive safety culture was that an ‘effective method of hazard identification has been established’. The converse example ‘disabler’ of a positive safety culture was ‘no effort is spent on hazard identification’ (CASA, 2021).
Figure 27: Hudson Ladder
Source: Hudson n.d.
Helibrook’s safety management
Helibrook’s SMS manual had not been amended since initial issue and no meetings had been conducted since the introduction of the SMS. The safety manager described their role as ‘lacking’ and reported that most of their time was devoted to managing day-to-day operations (in their other role as Helibrook’s operations manager).
The safety manager also described the Helibrook hazard register as ‘a bit lacking’, with many of the listed items not actually hazards. Additionally, there was no assessment of risks, controls or mitigation strategies. Helibrook did not have or maintain a formal risk register, or any alternate means to track and identify hazards and associated controls for their operation. The safety manager also reported that no risk assessment had been conducted of any of Helibrook’s approved activities, including crocodile egg collection (an activity which the safety manager had not actually observed). The CASA instrument that approved human external cargo operations stipulated that human slinging could only be conducted if it was assessed as reducing the risk of heat exhaustion and/or crocodile attack. Despite that, there was no documented means of assessing the relative risks.
Safety equipment, maintenance and time to rebuild/overhaul were listed on the hazard register relating to ‘Helicopter’, however no risks had been identified with VH-IDW. The safety manager also reported being unaware that VH-IDW’s ELT was not installed.
The safety manager described Helibrook’s reporting culture as ‘not great’, with only one incident in Helibrook’s safety reporting system – a hard landing involving VH-XHB, which occurred on 30 August 2020, while the safety manager was at the site. In relation to that occurrence, the safety manager submitted an incident report to ATSB on 1 September 2020.
The report stated the pilot was the only person on board at the time of the accident. However, the ATSB obtained footage taken by one of 3 passengers on board at the time. The safety manager was nearby at the time of the accident and, despite the detail on the incident report, reported being unaware how many people were on board. The safety manager was also the Helibrook DAMP officer and had not requested drug and alcohol testing of the pilot following that incident, as they did not think the incident was sufficiently serious to warrant it. In response to that incident, the safety manager reported proposing a windsock be put in the area to assist pilots identifying the wind direction, as misidentification of the wind direction was assessed as a factor contributing to the incident.
The safety manager did not conduct an internal investigation into the accident involving VH‑IDW and several months after the accident reported that they did not know what happened, had not seen the aircraft or been able to obtain any information about it. As the DAMP officer, the safety manager had also not requested testing of the accident pilot.
Helibrook operations manual
CASA first assessed and accepted the Helibrook operations manual in December 2016. The Helibrook operations manual version 7.3 was accepted by CASA on 28 February 2020. The manual included a standard operating procedure (SOP) for crocodile egg harvesting. That SOP was approved by CASA on 11 June 2020. CASA’s approval of the slinging operation was based on reducing the overall risk of crocodile attack and heat exhaustion. The SOP stated that the primary reason for slinging personnel was to:
reduce the risk of heat exhaustion of personnel in extremely difficult terrain and high humidity temperatures.
It further stated:
Should heat exhaustion or fatigue be a factor in collecting the nest then the nest shall be collected by other means other than using a Sling person.
The intent of the latter statement appeared to be to avoid operating in and around a helicopter if personnel were affected by fatigue.
One requirement of the procedure was for the chief pilot to have briefed the pilot before the pilot was permitted to conduct HEC sling loads. The briefing was to include a minimum 30-minute oral brief, a minimum 30-minute equipment demonstration/inspection and a minimum of 1 hour flying time. This was to be documented on a pilot competency check form. There was no record this had been conducted for the accident pilot.
Additionally, Helibrook did not have documented training for the pilot to conduct HEC slinging operations, or evidence that the pilot had trained in Helibrook’s emergency procedures for HEC slinging. The pilot reported having demonstrated some criteria and conducted ergonomic testing of the switches with CASA, but could not recall specific training by the operator. At the start of each season, the pilot completed annual administration and recurrency with WHNT but no helicopter-based training specifically for the activity.
The pilot reported that they did not generally practise emergency procedures for slinging. In their most recent operator proficiency check, the pilot recalled conducting autorotations and other emergencies. They did not practise releasing the sling load, as the pilot reported doing it ‘every day’ and it was ‘just two pushes of the buttons’. The chief pilot reported that it was ‘too dangerous to put yourself in an autorotation in that scenario to practise’, but they did general emergencies/autorotations as part of the training.
The SOP included ‘Safety aspects to consider before approaching a nest’. It required pilots and sling persons to assess slinging access to the nest including consideration of timber, trees and obstacles. It stated: ‘Should there be obstacles that will affect the safe operation then the sling option will be abandoned’.
Pilots were also required to be ‘fully conversant’ with the CASA instrument (approving use of HEC for crocodile egg collection) including the conditions and limitations. The requirement for the pilot to brief the crew/sling person on the emergency procedures was included.
Emergency procedures for crocodile egg harvesting
Helibrook’s standard operating procedure
The SOP included the following section titled Emergency procedures:
The pilot shall brief the crew on the emergency procedures in the event of an aircraft failure. The pilot, crew and Sling Person shall together discuss that in the event of an engine failure, aircraft strike or any other type of incident the pilot may need to release the Sling Person. The Sling Person shall have a clear understanding of the risk involved and the implications of such an emergency. Providing all height and speed limitations are being adhered to the risk of injury in the event of an emergency will be reduced.
Both the pilot and Sling Person shall carry personnel emergency locator transmitters during all operations. The aircraft shall have a satellite phone on board at all times and all personnel are to be briefed on its use.
Prior to any Sling Person being slung, the pilot in command must advise the Sling Person of the high risk nature involved in sling operations with an aircraft in the high hover state and the potential for injury or death should there be an equipment failure.
In addition to the Company standard passenger brief the Chief Pilot or approved pilot in command shall brief the Sling Person on the possibility of an emergency happening and what steps shall be taken to reduce the risk to persons involved.
The following emergency procedures were then specified:
Partial engine failure malfunction
The pilot in command shall attempt to place the Sling Person on the nearest safe area and release the strops from the aircraft
The aircraft shall proceed to land at the nearest suitable area
Complete engine failure
The pilot in command shall release the Sling Person as close to the ground as practicable and attempt the cushioning of the aircraft onto the ground, forward of the Sling Person and clear
Note:
At any time that a Sling Person is on the strop (long-line) he / she shall not be any more than five (5) m above the immediate ground and or vegetation
Should an engine failure occur the aircraft will already be in the high hovering state which is outside a safe auto-rotational envelope therefore the pilot will only be able to cushion the aircraft the best he / she can
The Sling Person shall do his / her best to move away from the aircraft or where the aircraft is coming to rest
Training in emergency procedures
Planning for emergency procedures is a critical component of risk management in HEC operations (DOI, 2010). A study into the human factors aspects of human external loads recommended that all HEC crewmembers be initially and continually trained and practised in emergency procedures (Shehab, Schlegel & Palmerton, 1998). For any in-flight emergency, training is essential to ensure a pilot responds quickly and appropriately. The FAA General Aviation Joint Steering Committee’s Safety Enhancement Topic – Emergency Procedures Training (FAA, 2013), stated:
Every pilot needs to prepare for the unexpected. Engine failures and inflight emergencies have a nasty habit of cropping up at the most inopportune times. However, with the right training and preparation, you can be ready for any hazardous situation that comes your way.
In the event of an engine power loss while operating in the H/V avoid area, a safe outcome is not always possible, and a pilot has very limited time to respond to achieve the most effective autorotation possible. In the event of a power loss with an external load, the decision to release a load is dependent on the load characteristics. For non-HEC, the load would be jettisoned to reduce aircraft weight, prevent the load from interfering with controllability and increase survivability of the helicopter’s landing.
For HEC, the pilot must decide whether to put the sling person on the ground or to release them. If the sling person is placed on the ground at a speed that minimises their risk of injury, the helicopter will descend rapidly from the height of the length of the sling line, increasing the pilot’s injury risk. The pilot’s injury risk is reduced as the impact velocity decreases. The minimum rate of descent of an R44 II helicopter in an autorotation is achieved at 55 kt airspeed. A sling person would be unlikely to survive an autorotation to the ground with that combination of vertical and horizontal velocity.
Although the Helibrook SOP permitted a sling person to be carried up to 5 m above vegetation (including trees), releasing the sling person more than 5 m above the ground is likely to result in fatal injuries. Additionally, release of the sling person with any horizontal velocity may make it difficult for them to remain erect, increasing the risk of landing other than feet first and increased injury severity.
Release of the sling person
The CASA-approved RFMS stated that survivability of HEC personnel during an in-flight emergency was best accomplished by having the sling person remain attached to the helicopter, unless they were snagged on terrain or likely to become so. However, the Helibrook emergency procedure in the event of engine failure stated that the pilot ‘shall release the sling person as close to the ground as practicable’.
CASA’s instrument approving HEC for crocodile egg collection required pilots to comply with both the RFMS and the company operations manual, and the onus was on the helicopter operator to ensure there was no discrepancy between the 2 documents. When asked about the discrepancy between the RFMS emergency procedure to keep the HEC attached to the line and Helibrook’s emergency procedure to release the HEC, the accident pilot reported that the RFMS stated it was the pilot’s discretion whether to jettison the HEC in the event of an engine failure.
The pilot commented that they ‘did not agree with’ the RFMS procedure to leave the sling person connected in the event of emergency, as that was ‘not a good method at all’. The pilot further commented that with a complete engine failure when operating above trees, if they left the HEC attached to the helicopter, the helicopter would either descend 100 ft vertically on top of the sling person, or the sling person would be dragged through the trees.
The chief pilot advised that in the event of an issue with the helicopter with HEC the pilot would flare the helicopter to try to ‘get the sling person off safely’, and in doing so, sacrifice themselves (and the helicopter) because they would lose rotor RPM. They further stated that in the event of engine failure while slinging, they would likely have their head out the door (watching the sling person) and would look in at the cockpit instruments and identify what had happened. The pilot reported that if they had forward speed, they would flare to release the sling person as safely as possible, then nose forward to try to regain airspeed before flaring the helicopter onto the ground.
Operating height
The Helibrook emergency procedure stated that the HEC ‘shall not be more than 5 m above the ground and or vegetation’. The accident pilot reported that when slinging with HEC, they tried to minimise the height and distance, and the sling person would usually be just above the treetops. The chief pilot also reported that they would go over trees and another pilot who had previously conducted crocodile egg collection reported that the SOP requirement to be not more than 5 m above the ground or vegetation was interpreted to include not more than 5 m above 30.5 m (100 ft) trees. One of the other operators conducting crocodile egg collection reported that they had normalised operating above treetop height, and had removed the height reference from their operations manual. The amendment to that operations manual had been accepted by CASA.
Operating above trees increased both the height of the fall if the sling person was released and the likelihood of having to release the sling person to prevent entanglement with vegetation rather than place them on the ground.
R44 human external cargo operations
Requirements for human external cargo operations
A CASA-authorised aeronautical (design) engineer first issued an engineering order approval for installation of a hook system on an R44 helicopter in December 2007, to enable slinging of an egg collector onto a crocodile nest to facilitate egg collection. However, the approval for fitment of the hook system did not in itself provide approval to conduct external load operations. To make it clear that operational approval was also required, the RFMS associated with the engineering order for the hooks system stipulated that use of the hooks was limited to the commercial collection of crocodile eggs in accordance with CASA-approved operational procedures.
CASA authorisation
Civil Aviation Regulations 151 and 250, which were in force throughout the 2007–2021 period of instrument approvals, did not permit a person to be picked up or carried outside a helicopter without CASA’s authorisation and permission. For crocodile egg collection, CASA issued instruments to helicopter operators that authorised the pilot in command to pick up a person under Civil Aviation Regulation 151(3) and permitted the pilot to carry that person in a harness system attached to the R44 helicopter under Civil Aviation Regulation 250(2). Civil Aviation Safety Regulations Part 11 applied to this authorisation. Specifically, CASR 11.055 (1)(d)[20] stated that CASA may grant the authorisation only if ‘granting the authorisation would not be likely to have an adverse effect on the safety of air navigation’ (CASR, 2010).
Key safety considerations
For the helicopter and pilot (and any other occupants), the key risk that results from carrying (slinging) a person under the helicopter is an event in which the HEC becomes entangled or a similar scenario that may cause a loss of control to the helicopter. Additionally, slinging involves operation in the H/V avoid area, and carries similar hazards to the helicopter and occupants as any other operation in that flight regime.
As the sling person is outside the protection of the helicopter, consideration is required of the likelihood of any scenario where they may collide with an obstacle or the ground, such as a fall resulting from deliberate or inadvertent release of the hooks.
Certification of dual hooks for HEC
Certification requirements
In 2013, CASA identified that the hooks that were being used for crocodile egg collection operations were not certified for HEC. The premise for the certification of any jettisonable external load was that it could be released, without exceptional pilot skill, to prevent hazard to the aircraft, such as causing a loss of control. For HEC, in addition to the need to be able to rapidly release the load to avoid a hazard to the aircraft, it was also necessary to minimise the probability of inadvertent release.
The design engineer then commenced a process to enable the hooks to be approved for HEC by meeting the certification requirements of US FAR 27.865. Compliance was demonstrated except for the requirement that the hooks would not open uncommanded and release the HEC or fail to release, due to electromagnetic interference (EMI). Given limited time until the crocodile egg collection season started that year (December 2013), CASA approved the design engineer to continue to authorise installation of the dual hooks under the engineering order with an interim approval exempting compliance with the FAR EMI requirement until March 2014. The operation continued to be conducted in accordance with a separate CASA operational approval (instrument).
Equivalent level of safety
About 12 months later (after the March 2014 deadline had passed), the design engineer advised CASA that the EMI testing had not been carried out and sought an equivalent safety determination[21] for the requirement. The basis for the proposed equivalent level of safety was that the operational limitations for HEC specific to the egg collection role ‘reduce the risk to equivalent or less than that of a system showing compliance’. That is, there would not be an unacceptable level of risk to the sling person if the hooks released due to EMI while the sling person was on the line, or to the pilot and helicopter if the hooks failed to release due to EMI.
A suite of supporting documents was supplied to CASA, including one that documented operational conditions to reduce exposure to EMI. Another key document proposed limitations to the height the HEC could be carried, to reduce the consequences in the event of release of the sling person due to EMI.
HEC height limitations
In approving crocodile egg collection operations with HEC, CASA had imposed speed and height limitations – that the HEC was to be carried at walking pace and not more than 5 m above the ground or obstacles. The HEC height limitations document relating to EMI risk proposed that those conditions already in place would provide an equivalent level of safety to compliance with the requirement that EMI must not result in release of the hooks. The report concluded that the proposed limitations provided ‘a strictly controlled level of risk for the HEC person in crocodile egg collection operations’. The proposed limitations included ‘a speed not exceeding walking pace’ and that:
a height limitation of 5 metres be imposed. In the alternative if this is unacceptable to CASA a height limitation of 5 meters above water or swampy terrain and a height of 3.3 meters above hard ground be imposed.
The report referenced scientific studies into injuries and mortality due to falls from heights. These studies identified a significant increase in the likelihood of mortality associated with:
falls from heights above 5 m
increased age
landing other than feet first
head injury.
Based on these factors, the report noted 4 conditions associated with crocodile egg collection that mitigated against the risk of injury in falls from heights. These were that:
only fit, young persons were employed
any release would have the person in the best orientation, normally erect, and a maximum of three body lengths above the ground, minimising the time for the orientation to be upset
In October 2015, a new hook wiring design was bench tested and the 28 Volt electrical system was found compliant with the EMI requirement. At that time, CASA requested the design engineer lodge an application for the hooks to be fitted under an STC.
In the same month, the design engineer provided CASA with a compliance report detailing assessment of the R44 dual hook for HEC installation with FAR 27.865 – External loads. Demonstration of the reliability of the system included completion of a Failure Modes and Effects Analysis,[23] showing that all potential failure modes of the QRS that may result in catastrophic failures, serious injuries or fatalities were extremely improbable (in the order of 10-9 or less), and any less significant failures were improbable (in the order of between 10-7 and 10-9). The FAA Advisory Circular (AC) 27-1B regarding Reliability of the external load system, including QRS, stated:
(ii) Any failure mode of the external load system (including QRS, hook and attachments to the rotorcraft) leading to a loss of the HEC should be considered a Catastrophic event….
In meeting all requirements of FAR 27.865, failure of the hooks resulting in the release of the HEC or failing to release were assessed as extremely improbable. These therefore met the defined acceptable (tolerable) level of safety. Having conducted the analysis for failure modes of the hooks, the design engineer described helicopter engine or control loss as ‘the most significant risk for this operation and can only partly be ameliorated’. Further, that the ‘only amelioration which can be applied is’:
5.2.1. Maintaining a high level of airworthiness of the helicopter. CASA have specified a power check prior to each operation, but it is possible stricter control of maintenance processes mat [sic] assist.
5.2.2. Training of persons involved, although options for personnel control of events are extremely limited in this failure mode.
Instrument conditions
Purpose of the conditions
In granting an authorisation to conduct HEC, CASA could specify conditions that were required to be complied with when operating under the authorisation. These were stipulated in an authorisation instrument. CASA delegates stated that the instrument conditions were designed to mitigate the risks of the activity.
Previous CASA instrument conditions
The first CASA authorisation instrument for R44 HEC for crocodile egg collection, was reported to have been issued in 2007 associated with the first fitment of a hook system to an R44 helicopter for HEC. CASA was unable to find any record of instruments issued prior to 2010 or any documented safety case or risk assessment associated with the first instruments that were issued for the activity.
The ATSB obtained instruments issued to several operators from 2010 to 2021 and interviewed several CASA delegates who had approved instruments for the activity, or were involved in the approval process from 2013 onwards.
The 2010 instrument was issued for both R44 and Bell 206 helicopters. All subsequent instruments were for R44 (and R44 II) helicopters only. The 2010 instrument listed 20 conditions, most of which appeared in all subsequent instruments. Included in the conditions were limitations to the height, speed and distance the sling person could be carried. Appendix C – HEC height, speed and distance/time conditions 2010–2021 includes a table of the HEC limitation conditions in the instruments issued from 2010 to 2021.
For the instruments issued from 2010 to 2013 (inclusive), these conditions were:
The person is not lifted to a height of greater than 5 metres above the ground or obstacles.
The aircraft is not flown at a ground speed greater than walking pace when the person is carried under the helicopter.
The maximum distance the person is carried under the helicopter is 500 metres for each pick up.
Request for changes to conditions
In 2013, one operator requested an amendment to the conditions, including replacing HEC height, speed and distance limits with pilot-assessed safe height, speed, and distance. In response, CASA asked the operator to conduct a risk assessment.
Operator risk assessment
That operator provided CASA with an assessment of risks identified for human sling operations for crocodile egg collection. The assessment was derived from a WHNT safe work method statement provided to all operators involved in the crocodile egg collection. The assessment detailed 7 steps in the job sequence. For each of those, it identified ‘What can go wrong’, assessed the initial risk, proposed control measures and assessed the resulting risk.
The job sequence ‘Lift collector and transit to crocodile nest’ obtained an initial risk rating of ‘catastrophic’. The likelihood was assessed as ‘very possible – will probably occur in most circumstances’; the consequences were assessed as ‘extreme – fatality or multiple fatalities’.
The list of hazards for that risk included equipment failure, falling from height and external load limitations (along with crocodile attack, adverse weather, fatigue/heat exposure/exhaustion, flora and fauna). The risk was reduced to ‘high’: unlikely – could happen sometime, with extreme consequences of one or multiple fatalities, with the following proposed mitigations:
• First Aid/trained personnel
• Medivac
• Pilot is spotter for people on ground, must ensure direct line of sight to human sling person at all times
• Collection crews in 1-2 man teams – lookout
• Pre-start inspections include belly hook & longline test
• Collecting crew to inspect harnesses, helmets, radios
• Training/Experience
• Rehydration available
• Lift register
Engine mechanical failure and fuel exhaustion/starvation were not included in the hazards for the slinging component therefore no relevant mitigations were included. Engine mechanical failure was however identified as a hazard in the non-slinging job sequences ‘Start aircraft and take-off’, Fly/Ferry to collection areas’ and ‘Return to base/ferry to next job’. Mitigations for engine mechanical failure included the daily inspection, emergency training and rescue plans, adherence to helicopter limitations, and pilot training/experience.
The CASA delegate who assessed the provided risk assessment described it as basic and the requested condition changes were not granted. However, there was no documentation provided that correlated the risk assessment with CASA’s retention of the conditions in the instrument.
2014 and 2015
The 2014 and 2015 instruments were valid from December to the following May, consistent with the crocodile egg collection season. In 2014, the 2013 condition that limited the HEC height to 5 m above the ground or obstacles was amended to:
The person is not to be lifted to a height of greater than 5 metres above the ground or water. To remove doubt this instrument does not permit lifting of a person to a height greater than 5 metres above an obstacle. The height restriction is in reference to the ground or water in all instances.
No documented reason for amendment to the operating height conditions was provided. The delegate who made that amendment reported that the purpose was to make it clearer and avoid ambiguity. The delegate also amended the speed condition to be less prescriptive and provide ‘flexibility to operate more safely’. The HEC speed limitation was changed from ‘walking pace’ to:
The aircraft is to be flown at speed that is considered by the pilot in command to be a safe speed, taking into consideration the prevailing wind direction, wind speed, and aircraft performance when the person is carried under the helicopter. Minimisation of injury to the person in the event of hook release (whether planned or inadvertent release) must be considered in the context of the total forward speed of the person over the ground.
A new condition was also added in the 2014 instrument, which stated that the sling person must be provided with a copy of the instrument and ‘made aware, in writing, that the hook system is not certified for human use’. That condition was retained in all subsequent instruments.
2016
In 2016, the CASA delegate was invited to a demonstration of human slinging for simulated crocodile egg collection. Following the demonstration, the height condition was amended to provide the operators ‘some relief to be able to go over obstacles that might be in their flight path to go from one point to another’ as follows:
The person is only to be lifted to a height above the ground or water that enables the person and aircraft to safely traverse over natural obstacles. In all other instances, the person is not to be lifted more than 5 metres above the ground or water. Minimisation of injury to the person in the event of hook release (whether planned or inadvertent release) must be considered in the context of the height the aircraft is operated above the ground or water at any particular time.
When asked how lifting the HEC above the nominal survivable height of 5 m affected the activity risk, the delegate commented that it was not un-survivable because ‘the operator had an obligation to conduct the operation in a safe manner’. Additionally, in 2016, the 500 m distance limit the HEC could be carried was amended to:
The person is only to be carried for the minimum distance and time required in order to safely conduct the activity, taking the possible effects of suspension trauma on the person into consideration. To avoid any ambiguity, the intent of this condition is that the person is not to be carried for the purpose of positioning flights over landing sites where it would be possible to conduct the safe donning or removal of the person from the strop used to carry the person.
In 2016, Helibrook received their first instrument for R44 HEC for crocodile egg collection. The chief pilot had previously been involved in conducting the same operation for different AOC holders.
2017 and 2018
The ATSB obtained instruments issued to 3 operators in 2017, including Helibrook. As Helibrook was oversighted by a different CASA regional office to the other operators, multiple delegates were involved in the instrument approvals.
Late in 2016, the EMI test report demonstrating compliance of the hook system was completed. As a result, the HEC height limit was removed from the RFMS for the hooks, which was only required to consider failure of the hook system, not failure of the helicopter and associated operational safety limitations. A 60 kt speed restriction was included in the RFMS, based on reported feedback from an egg collector stating that was a suitable operating speed. It was noted at the time the amendments were made to the RFMS, that operational limitations specified in CASA’s operational instrument would be ‘overarching and could contain more conservative limitations’. However, when CASA asked for advice regarding limitations, the design engineer advised that additional limitations were unnecessary as the system was now HEC compliant.
The 2017 delegates and their CASA subject matter experts – airworthiness/engineering and the previous delegate – agreed that as the height limitation had been removed from the RFMS, it could also be removed from the CASA instrument, because inadvertent release was now extremely unlikely as the hook system was compliant. It was also assessed that there was no longer any purpose in stipulating a speed limit because ‘at 500 ft above ground level…forward speed will have no bearing on the HEC’s chances of survivability’. Therefore, the height limitation condition and the clause in the speed condition regarding minimisation of injury to the HEC were removed from the 2017 instrument conditions. However, the pilot-assessed safe speed and minimum distance conditions were retained.
The delegates reported that they relied on information provided by the subject matter experts and assessed that there were reasonable mitigations in place with the conditions. One delegate reported that they had accessed relevant files and had conversations with other delegates. They therefore assessed that the activity presented an acceptable risk, particularly as the instrument was a renewal for an activity that had been conducted without accident or serious incident for at least 5 years.
Although the height and speed limit conditions were removed once the hooks were HEC compliant, the instrument condition advising that the hooks were not certified for human use was retained. The delegate reported that their understanding was that the hooks were satisfactory and fit for purpose but not certified or approved by CASA.
The instrument delegate responsible for the instrument issued to Helibrook assessed that the activity was high risk, but accepted by CASA. Further, they considered that the removal of the height limitation was ‘a small change’ and nothing significant that would affect the operation.
From 2018, the instruments were issued for a 12-month period from December.
2019 and 2020
The CASA flight operations inspector responsible for oversighting Helibrook was assigned as the delegate for Helibrook’s instrument renewal in 2019 and 2020. The delegate assessed that the Helibrook operations manual had reasonable procedures for the activity, the sling equipment was approved, and the chief pilot and/or pilots involved had sling approval and relevant experience.
The delegate assessed that as it was a renewal, the procedures were in place and if they continued doing what they were doing previously, there was probably no reason not to allow them to continue what was an established activity. They also assessed that minimisation of exposure was included in the operator’s procedures. The delegate did not identify any discrepancies between the operations manual, RFMS and the instrument conditions.
In both of those instruments, CASA’s STC approval process of the hooks was underway. In anticipation of that approval, the conditions included that the aircraft must have been modified in accordance with the nominated engineering order for the dual hooks, but would need to be shown to be compliant with and certified to the STC within 14 days of the STC’s approval.
Delegate guidance material
In an email to the ATSB, CASA reported that there was no ‘granular documented process’ for approving instruments like the R44 Dual Hooks for HEC for Crocodile Egg Collection authorisation. The CASA Air Operator’s Certificate (AOC) Process Manual included a section on CASA approvals and exemptions, with a process map and the administrative steps required. Additionally, CASA’s Air Operator’s Certificate Handbook provided detailed information for assessing and issuing an AOC, including:
process overview
assessment criteria, methodology and link to checklists for AOC approvals
operational personnel
inspection of specialised equipment fitted to aircraft
assessing an operations manual
volume 2 provided guidance for assessing an application to include an aerial work purpose on an AOC, which included appropriate operations manual content, inspection of specialised equipment and review of the chief pilot's experience and qualifications
volume 4 included assessing safety management systems with a sub-section on safety risk management, which included guidance to assure an acceptable level of safety existed.
The CASA delegates approached by the ATSB reported that the AOC‑related documents provided broad or generic guidance, and while similar principles could be used for assessing a request for an authorisation and permission instrument, they did not contain specific relevant guidance.
Safety assessment
To determine how CASA delegates assessed that safety was preserved when issuing authorisations, the ATSB requested detail of any risk assessments associated with the instruments. In response, CASA advised that they could not locate any risk assessments and that they had not conducted any specific testing or assessment of the risk profile for the activity of R44 HEC for crocodile egg collection. Specifically, CASA also advised that they had no evidence of any risk assessments associated with the instruments issued to Helibrook between 2016 and 2021.
CASA required a request for an authorisation to be made in writing and when assessing a request, delegates relied on the advice of other CASA personnel with subject matter expertise and experience. This advice was generally communicated by emails, some of which were filed in the records management system, or by telephone. The assessment was then made based on judgement of the activity’s reasonableness, but there was no documented acceptable risk level.
Although they reported not having seen a CASA risk assessment for the activity, the involved delegates assumed that a safety case would have been provided with the first operator’s request for approval for the activity (sometime prior to 2013) and that had been assessed and accepted by CASA. The activity was understood to be high risk, but delegates believed that CASA accepted that risk level. In particular, as the 2013 instruments were signed by a senior CASA manager, this was interpreted as an endorsement that it was appropriate to continue issuing the approvals.
Additionally, the annual approvals for operators were considered to be reissues of instruments for a previously accepted activity, albeit to varying helicopter operators. All the operators conducting crocodile egg collection each season received essentially the same instrument, although some conditions varied from one year to another. Prior to issuing Helibrook’s first instrument in 2016, a CASA inspector verified that the operator had:
a procedure for conducting the activity
appropriately experienced personnel
relevant documentation and sling equipment.
For an annual issue of an instrument to an operator who had previously held the authorisation, the delegate’s primary check was whether there had been changes to procedures or personnel since the previous issue. The delegates reported that if there had been no changes to procedures, and no enforcement action taken against an operator, they had no reason not to reissue the instrument. Additionally, as mentioned above, they assessed that the activity was being done safely as there had been no reported accidents or serious incidents.
The delegates all reported that the instrument conditions were intended to mitigate the risks associated with the activity, and that they assessed there were sufficient conditions and procedures in place to mitigate the risk to a reasonable level. Additionally, they considered that there was an onus on the operators to act safely and to advise CASA, via their operating procedures, how they were going to reduce the associated risks.
Human external cargo rotorcraft load combination decision
In August 2013, a CASA project was initiated to consider existing HEC regulations and propose amendments to Civil Aviation Order (CAO) 29.6, which only applied to non-human sling operations. The project identified that permissions being issued by CASA regional offices were not issued on the basis of a risk assessment or reflective of international standards. Specifically, in the US, United Kingdom and Canada, HEC was not permitted with piston engine rotorcraft and, CASA had assessed that the use of piston engine helicopters increased the risks to HEC compared with turbine engine rotorcraft. Additionally, in 2013, helicopter operators involved in the powerline industry had approached CASA for HEC approval using turbine engine rotorcraft, consistent with international requirements.
As a result of the project, in October 2013, the then CASA Director of Aviation Safety (DAS) signed an internal minute that recommended CASA restrict HEC operations to the following requirements:
single engine turbine powered rotorcraft with a usage monitoring system
out of ground effect hover performance with a performance buffer
restrictions on who could be carried
an attachment means certified for the carriage of humans.
The minute also recommended that the proposed standard be communicated to CASA field officers for consideration in all authorisation/permission approvals, while the proposed amendment to CAO 29.6 to reflect the policy was being drafted.
As a component of the project, a CASA risk workshop on crocodile egg collection using HEC was held on 20 November 2013. While no minutes were recorded from the meeting, a draft risk management plan (RMP) provided to the ATSB formed the basis of the discussions.
Risk management plan
The stated purpose of the RMP was:
to examine the risk indicators in HEC operations in a piston engine rotorcraft in an Australian operational context of crocodile egg harvesting.
The RMP was drafted by a senior standards officer with significant helicopter and HEC expertise using a CASA general aviation operations template. The scope included that the assessment:
…considers isolated factors specific to piston engine rotorcraft, single engine turbine rotorcraft and multi-engine turbine rotorcraft. Risks relevant to the task of HEC beneath any rotorcraft are examined for context and amplification. A limitation to scope is that the cumulative effect of the individual risks should they be realised in combination is not considered. It would be prudent to conduct analysis of this eventuality should the risk assessment be furthered.
The assumptions listed in the RMP were:
• Permitted operators must have a proven safety and compliance record underpinned by a robust Safety Management System that could be leveraged for continued operation with strict regulatory oversight.
• CASA will exercise additional oversight of approved operators should an approval be granted that is strictly limited in scope and will result in removal of the operators [sic] approval should any non‑compliance be identified.
• The risk exposed by utilizing an external load assembly not approved for HEC provides a residual risk rating that is acceptable for a finite period of six months.
The overall operational risk of the activity was assessed with an initial risk rating of high (7), which ‘needs senior management attention’, and the residual risk (with controls in place) of medium (5), requiring ‘management responsibility’.
CASA’s General aviation operations group risk matrix utilised to assess the operational risk is depicted in Appendix B – CASA operational group risk matrix (2013). Extreme and high risks were required to be reported to senior management and have detailed treatment plans, ‘which reduce the risk in accordance with the ALARP [as low as reasonably practicable] principle’. CASA AC 138-05 – Aerial work risk management defined ALARP as ‘the point where the costs of introducing further safety measures to lower a risk outweigh the safety benefit. However, a risk should be tolerated only if there is a clear benefit such as a compelling operational need’ (CASA, 2022).
The broad risk categories considered in assessing the risk associated with HEC operation were:
engine failure/malfunction inside the H/V envelope with HEC attached
insufficient excess power available for role and environment
equipment/hardware failure of rotorcraft system or subsystem
human error while undertaking HEC operation.
Potential risk controls were:
preference of multi engine turbine rotorcraft with [one engine inoperative] OEI accountability
preference to single engine turbine rotorcraft
usage monitoring systems of pertinent parameters
equipment standards to HEC design criteria
limitation of exposure measured in time, distance, speed and height [above ground level] AGL
CASA increased surveillance of operations whilst under limited conditions
CASA mandated minimum experience level and qualification to conduct HEC
increased engine and critical component inspection criteria
mandated excess power margin requirements for [hover out of ground effect] HOGE conditions
limitations in environmental conditions including wind azimuth, velocity, humidity.
The RMP identified 26 individual hazards, all of which were assessed as initially not ALARP. Some of the documented hazards were linked to the R44 POH and Robinson Safety Notices. Proposed operational mitigations included additional regulatory oversight to ensure procedures were followed and maintenance/overhaul requirements were adhered to.
For the hazard of single engine piston rotorcraft engine failure while operating in the H/V envelope, the likelihood was assessed as rare – 1 in 10,000 to 1 in 100,000, with severe consequences – multiple life-threatening injuries/less than 10 fatalities, and an overall medium risk. Suggested mitigations to reduce the residual risk, still rated as medium, included:
minimise exposure time for HEC and enforce conservative limits of distance, height and time
require engine usage monitoring system
use fuel injected models only
require single engine turbine to reduce failure rate, or multi-engine rotorcraft with one engine inoperative accountability; or in consultation with the manufacturer increase inspection requirements including engine compression checks, and reduce overhaul period.
There was no assessment of the hazard of fuel exhaustion, but fuel starvation or contamination was assessed. For these, the initial risk was assessed as unlikely, and the consequences were severe with an overall high risk rating. With mitigations including fuel checks, minimum fuel requirements, fuel usage policy and turbine engine, the residual risk was medium, requiring CASA management responsibility.
The author of the RMP subsequently advised the ATSB that the omission of fuel exhaustion as a hazard was unintended, and that the proposed mitigations were also applicable to fuel exhaustion.
CASA’s Flight Standards Branch advised the ATSB that the RMP was never finalised, and the risk controls proposed to mitigate the risks of continuing R44 HEC for a further 6-month period were not implemented. The draft RMP was however used by CASA Flight Standards Branch to propose HEC standards, first for an amendment to Civil Aviation Order 29.6, which was subsequently discontinued (in 2016), and then for the development of CASR Part 138.
CASA also advised that the RMP was used to consider the potential viability of allowing single engine piston helicopter HEC operations based on an equivalent level of safety. This would have required demonstration that the piston engine helicopter had a similar in-flight failure rate as a turbine engine helicopter with a usage monitoring system. Members of CASA’s Flight Standards Branch presented this option to operators in 2014, however, no operator attempted to demonstrate this equivalence.
Intent to amend approval conditions from 2014
On 6 December 2013, CASA’s operations division sent a letter to an operator that had previously been authorised to conduct R44 HEC operations. The letter included the proposed future position requiring single engine turbine power rotorcraft with a usage monitoring system and other requirements as per the revised policy position approved by the then DAS. The letter stated that CASA had:
reviewed a number of risks and hazards in human external cargo operations, particularly when conducted by single-engine piston rotorcraft that resulted in unacceptable risks particularly to the person being slung.
The letter then detailed the relative risks of single engine piston rotorcraft compared with single engine turbine rotorcraft. This included detail that in the US from 2004–2008, the accident rate of single engine piston rotorcraft on average exceeded 1 per 10,000 flight hours and was more than 3 times that of single engine turbine rotorcraft. Engine failure inside the H/V envelope was identified as one of the main risks related to single engine rotorcraft. It also listed other known failure modes of R44 rotorcraft that had been identified in the RMP.
In summary, the letter advised the operator that CASA intended to renew the authorisation with some changes to the conditions for one more season before turbine engine rotorcraft would be required. At the time, the cargo hooks were not certified for HEC and a proposed condition was that the authorisation did not override engineering or airworthiness limitations.
Response to the proposed changes
The design engineer responsible for the hooks system responded to CASA’s letter on behalf of operators that conducted crocodile egg collection. The response disputed the safety data referenced in CASA’s letter, requested coordination between CASA’s certification/airworthiness and operations personnel and continued R44 operation for one more season to allow operators time to address the proposed requirements.
In response, a CASA regional manager made a documented recommendation to a senior manager within CASA that R44 HEC operations continue. The recommendation outlined CASA’s authorisations of R44 HEC operations for crocodile egg collection, the 2013 DAS decision to establish formal policy (including the use of turbine powered rotorcraft for human sling load operations) and that since that decision, CASA had undertaken work regarding the appropriateness of piston engine rotorcraft to carry human external cargo.
The recommendation also advised that that operator had requested reissue of the authorisation to continue to operate until CAO 29.6 changes were finalised. In support of the request for continued R44 HEC operations, the design engineer provided their comparative analysis of Bell 206 (turbine helicopter) and R44 engine failure data. Additionally, the regional manager proposed that extra conditions be included in the instrument to ‘mitigate those risks further’. Key additional conditions from the precedent instrument (which was valid from 2 December 2011 to 31 December 2013) were:
the hooks are to be certified for use in human sling load operation
engineering orders must confirm that all things attached to the hook systems are fit for purpose
the aircraft is to be operated in accordance with the approved FMS
daily inspection includes sling system/equipment
the pilot is required to verify the engine is capable of normal rated power with no defects evident and to certify this on the maintenance release
only persons employed or contracted for egg collection can be carried.
The reasons given for the recommendation were that:
the overall risk to safety of the egg collector could be reduced by the use of the R44 aircraft type
other operational activities permitted by CASA possessed ‘equal hazards and risks, such as mustering operations, night agricultural operations, and parachuting activities’.
The senior manager agreed with the recommendation and signed instruments authorising continued R44 HEC operations for crocodile egg collection to the end of April 2014 for 2 operators.
The CASA delegate who approved the following year’s instrument assumed that one reason the 2013 instruments were signed by a senior manager was to demonstrate that CASA senior management was aware of the operational approvals process and was satisfied it was appropriate to issue the instruments.
Proposal to discontinue CAO amendments
In 2016, the then DAS agreed with a proposal from CASA Flight Standards Division to close the existing project to amend CAO 29.6, as it had been ‘superseded by Part 138’. The finalisation of Part 138 was reported to be ‘imminent’, with a proposed effective date of September 2018. The proposal included that crocodile egg collection would ‘continue as per current exemptions until such time as Part 138 is made and the regulation commences’.
Transitional regulations
At the time of the accident, Helibrook and other operators were conducting crocodile egg collection under their AOC as an aerial work operation. From 2 December 2021, crocodile egg collection required a CASR Part 138 Certificate (instead of an AOC) to authorise the operation. The crocodile egg collection operation (carriage of a person outside a rotorcraft) was categorised as an aerial work class D external load operation under CASR Part 138.[24] Chapter 15 of the Part 138 manual of standards (MOS) – Rules for external load operations, applied to the activity.
Section 15.06(3)(e) applied to rotorcraft that cannot hover out of ground effect with one engine inoperative, requiring section 9.05(b), (c), (d) and (e) of the MOS to be complied with. This required the rotorcraft to have:
a turbine engine
a usage monitoring system
control to be maintained in all phases of flight in the event of a hydraulics failure or alternatively dual hydraulics
redundant means of controlling fuel flow to the engine.
CAR 151 and 250 were repealed on 2 December 2021. An authority under CAR 151(3) and a permission under CAR 250(2) applied to CASR Part 138. The Part 138 requirements were more onerous than the existing instrument issued to Helibrook for crocodile egg collection, which permitted use of a piston-engine helicopter without a usage monitoring system. In order to permit continued egg collection using the R44 an exemption was granted under Division 11.F.1, including CASR 11.170(3), which stated:
In making its decision, CASA must regard the preservation of a level of aviation safety that is at least acceptable as paramount.
Despite the intended safety improvement associated with the introduction of Part 138 requirements, Helibrook’s instrument was issued on 9 September 2021, with a 3‑year validity period. Under the transitional legislation, it would cease at the earliest of the:
expiry of the instrument (31 December 2024)
second anniversary of the instrument commencement (7 September 2023)
day the operator’s AOC expired (31 July 2022, extended to July 2023 after the accident).
Considering these criteria, Helibrook would be required to comply with CASR Part 138 and Part 138 MOS when its AOC expired.
Briefing note July 2021
In July 2021, an internal briefing note to a senior CASA manager stated that:
When Part 138 of CASR commences on 2 December 2021, operators conducting crocodile egg collection operations will need to replace their Robinson R44 helicopters with a helicopter that has improved reliability.
The briefing note outlined the risk assessment and subsequent work, which had concluded that HEC operations were very high risk for the sling person. It stated that the risk could be substantially mitigated through the use of a turbine engine helicopter with a usage monitoring system. Additionally, the hook system needed to provide redundancy in the case of failure of the hooks/system.
The Background section of the briefing note included that CASA’s previous permission instruments had not been issued on the basis of a risk assessment, and that the risk had been assessed in 2013 as unacceptable without mitigation. Further, that CASA’s authorisation of R44 HEC operations was not reflective of international standards and significantly differed from the FAA, Transport Canada and EASA. At that time these organisations generally required multi turbine engine helicopters with one engine inoperative accountability for commercial operations, with the use of high-reliability single turbine engine helicopters permitted for limited specified operations.
The Way Forward section of the document noted that some helicopter operators were already conducting powerline maintenance work using a single engine turbine helicopter for HEC, based on the CASR Part 138 standards.
Helibrook’s 2021 instrument
The 2020 instruments were valid until 31 December 2021. On 2 September 2021, the Helibrook safety manager emailed CASA’s Regulatory Services requesting a renewal of the instrument with the 2020 instrument attached to the email. After payment, the task was assigned to the delegate on 9 September 2021, who recalled that it was relatively urgent. The delegate reported being unaware of the history of the authorisation, but was aware of the general risk of the operation and that it had been assessed by multiple sections within CASA.
The delegate reviewed the file relating to the most recent instruments and emailed the previous approver asking whether there were any concerns regarding reissue of the instrument to Helibrook. The previous approver advised that:
the STC for the hooks had been issued on 30 July 2021
there had been no changes to Helibrook’s equipment or procedures that they were aware of
CASR Part 138 was not yet in force
considering the above, they saw no reason why a new instrument should not be issued.
They also commented that they did not believe there was a compelling statistical argument to justify the higher cost of a turbine engine helicopter that would be required under Part 138.
The delegate then signed the instrument on 9 September 2021 with an expiry date of 31 December 2024. There was no change to the conditions from the previous year’s instrument. The references to the now redundant EO were not removed. Condition 23 stated that when the STC is approved, ‘all aircraft previously certified to the [engineering order] EO will be shown to be compliant with and certified to the STC within 14 days of the STC being approved, after which time aircraft certified only to the EO may no longer undertake this work’. Helibrook did not update the hook installation on VH-IDW to the STC. The delegate reported that they were unsure about whether the hooks had been certified. The delegate also reported being unaware of the implications of the impending Part 138 requirements when they issued the instrument for a 3-year period.
At the time of the accident, VH-IDW was operating under CASA Instrument CASA.CARRY.0163 Revision 1, issued to Helibrook and dated 7 September 2021 (2 days prior to it being assigned to the delegate).
There were 34 listed conditions that Helibrook and the pilot in command were required to comply with (Appendix D – Instrument conditions). There was no limitation specified for the HEC carriage height. Key conditions discussed previously included:
The pilot in command and sling person were required to have completed a course of training for the activity promulgated in the helicopter operator’s operations manual. The operator’s training course was to include not less than 1 hour of flight time and 1 hour of ground instructional time.
A thorough pre-flight briefing was to include actions to be taken by crew members during possible emergencies – the briefing was to be conducted in accordance with the briefing procedures in the operations manual.
The helicopter was required to be compliant with the STC SVR 541 and to be operated in accordance with the FMS, which details normal and emergency procedures associated with the activity.
The pilot and operator were required to comply with the relevant procedures in the company operations manual.
The pilot was required to have continuous and clear radio communications with the sling person throughout.
The pilot was required to fly the helicopter at a ‘safe speed’ and to carry the sling person ‘for the minimum distance and time required in order to safely conduct the activity’.
The sling person was required to wear an Australian Standard helmet (‘appropriate to the risks encountered during the activity’).
Prior to commencement of the activity each day, the pilot was required to verify that the engine was producing normal rated power output, and that no defects were evident which could lead to power reduction during those operations.
The sling person must be made aware, in writing, that the hook system is not certified for human use.
Engine failure probability analysis
US data
Data based on the Lycoming Service Reporting Database, National Transportation Safety Board Aviation Accident Database, FAA Service Difficulty Reports, and FAA Accident and Incident Database System from 31 December 2016 to 31 December 2021, found power loss rate (incidents per 100,000 flight hours) were 0.54 for the R44 and 0.11 for the R44 II. These helicopter types therefore met the EASA requirements[25] for ‘Helicopter operations without an assured safe forced landing capability’ engine in-service sudden power loss rate requirement of not more than 1 per 100,000 (1 x 10⁻⁵) engine hours in a 5-year moving window. For that data, where the cause of the engine failure was unknown, or where maintenance was identified as the reason for the failure, they were counted as 0.5 and 0 events respectively.
Australian data
A review of R44 and R44 II engine failure occurrences reported to the ATSB,[26] compared with flight hours for the period 2011 and 2020 showed the average engine failure rate was 4.4 per 100,000 flight hours. Unlike the power loss rate data above, these did not consider whether the failure resulted from maintenance or an unknown reason, which may account for the higher engine failure rate in Australia. Fuel exhaustion and fuel starvation were not coded as engine failures.
In addition to engine failures, the ATSB identified R44/R44 II accidents and serious incidents that occurred during the same period, which would likely result in injury to the sling person if they occurred during slinging operations. These were primarily losses of control and occurred at a rate of 2.8 per 100,000 flight hours. The combined rate of engine failure and other occurrence types likely to result in injury to the sling person was 7.2 per 100,000 flight hours.
At risk time
To quantify the risk of the activity, it was necessary to approximate the amount of time HEC was being conducted each year in Australia under a CASA authorisation. In the 2020–21 and 2021–22 seasons, 3 helicopter operators had CASA authorisation for R44 HEC operations to conduct crocodile egg collection. Of those, 2 contracted to WHNT and one operator supplied a different crocodile farm. WHNT provided total invoiced hours for 3 R44 helicopter operators for those seasons, one of which did not have a CASA instrument for HEC, but the ATSB obtained evidence from February 2021 showing dual hooks installed on their helicopter. In the 2020–21 season, 566.1 hours were invoiced and 507.3 in the following season, in which activities were suspended following the accident. This included the accident pilot, operating VH-IDW as one of the 2 HEC helicopters for WHNT, who had invoiced 21.5 full days of conducting crocodile egg collection for the 2021–22 season to 22 February 2022 (approximately 200 hours).
WHNT initially estimated that they were generally slinging about half the total engine-running time, and later revised this to about 20% of the total time for the 3 helicopters operating for WHNT. The other (non-WHNT) operator estimated they did about 15 hours of HEC each season.
Based on the information and approximations provided, the ATSB assessed the effect of slinging a person under an R44 helicopter for 200 hours per year. On average, an engine failure or in-flight emergency likely to result in an accident, would occur once every 69 years while slinging a person.
Exceeded maintenance intervals
Exceeding maintenance, inspection and overhaul limits, increases the probability of an in-flight engine failure. The Robinson R44 Maintenance Manual stated that it ‘is the operator’s responsibility to maintain a record of time in service for the airframe, engine and life-limited components…[an] hour meter is an acceptable means of recording time in service’. The manual included the warning that:
Components with mandatory overhaul times or life limits whose time in service is not reliably documented cannot be considered airworthy and must be removed from service.
Lycoming Service Instruction 1009BE – Time between overhaul (TBO) schedules included the warning that ‘Operation of an engine in a non-airworthy condition could result in loss of life, serious injury, and damage to property’. Additionally, the Lycoming operator’s manual included:
Neglecting to follow the operating instructions and to carry out periodic maintenance procedures can result in poor engine performance and power loss. Also, if power and speed limitations specified in this manual are exceeded, for any reason, damage to the engine and personal injury can happen.
Previous occurrences
HEC accident
On 11 May 2022, a Bell Helicopter Textron Canada 407 helicopter was conducting HEC training in Livermore, California, US. The helicopter was about 175 ft above ground level with a sling person on a 60-ft long line when the engine lost power. The pilot manoeuvred the helicopter and partially raised the collective when the sling person was about 15 ft above the ground (AGL) and cushioned them onto the ground. The sling person was uninjured.
The pilot then manoeuvred the helicopter away from the sling person and when about 10 ft AGL, raised collective and released the sling line. The helicopter landed hard resulting in substantial damage to the helicopter and serious injury to the pilot, who had to be extricated from the wreckage. At the time of publication of this report, the US NTSB investigation was ongoing however, the occurrence showed that in a helicopter with more main rotor inertia than an R44, it is possible to cushion the HEC onto the ground, but the ensuing autorotative landing can result in serious injuries to the pilot.
Fuel exhaustion happens when there is no usable fuel remaining to supply the engine/s.
Fuel starvation happens when the fuel supply to the engine/s is interrupted although there is adequate fuel on board.
The report stated that the ATSB received an average of 21 reports of fuel exhaustion or starvation occurrences each year. Fuel exhaustion occurrences were normally either the result of an error in pre-flight fuelling, or a number of seemingly minor aspects of fuel planning and management during the flight. Consideration of different fuel consumption rates depending on the activity being conducted and flight conditions is a key component of fuel planning.
The chance of fuel exhaustion is reduced if a pilot accurately determines the amount of fuel on board prior to starting, by cross-checking from multiple sources. These include fuel quantity gauges, dipsticks, totalisers/flow meters and calculations from previous refuels and fuel usage regularly checked for accuracy.
ATSB fuel exhaustion occurrences 2011–2020
The ATSB occurrence database held 54 fuel exhaustion occurrences for the 10-year period 2011‑2020. Considering the involved engine types, 49 were piston, 4 were turbine and 1 engine type was unknown. However, of the total aircraft, only 5 were helicopters, 3 of which had turbine engines and 2 were piston engine helicopters. Neither of the piston helicopters were an R44, but one of the occurrences involved a piston engine R22 Beta helicopter conducting mustering operations. Given the small data set, there was no significant difference in engine type for helicopter fuel exhaustion occurrences.
For 14 of the 54 occurrences, the total flight time of at least one pilot was recorded. Table 4 details the number of occurrences, the number of those where the total flight time of one pilot was known, and the median total flight time. The median total flight time of a pilot involved in a fuel exhaustion occurrence was 1,227 hours with a range of 20 to 14,500 hours. This suggests that experience is not a mitigation against fuel exhaustion occurrences.
Table 4: Fuel exhaustion occurrences 2011–2020, engine type (1 unknown), median and range of pilot total flight time (TT)
On 4 October 2010, a Robinson R22 Beta helicopter collided with the ground while conducting cattle mustering operations. The pilot was fatally injured, and the helicopter sustained substantial damage. The investigation found that the collision with terrain was probably a result of engine stoppage due to fuel exhaustion, while operating at low altitude. The investigation also found that:
The nature of mustering operations had the potential to divert the pilot's attention away from other safety-critical tasks, such as monitoring the helicopter's fuel state.
Long line fuel exhaustion accident
In 2012, the US National Transportation Safety Board investigated an MD Helicopters 500D helicopter accident, in which the engine lost power while a utility worker was suspended on a long line attached to the helicopter. The investigation analysis included the following:
The helicopter was in a hover about 120–150 feet above the ground while a utility worker performing a long-line operation worked on a transmission tower. After the loss of power, the helicopter spun and descended during which the worker was pulled off the tower by the attached long line. The pilot performed an autorotation that resulted in a hard landing. The pilot sustained serious injuries and the worker sustained fatal injuries.
Post accident examination of the helicopter revealed no usable fuel on board, and fuel quantities between the fuel tank and engine were consistent with fuel exhaustion. The examination revealed that the electrical wire to the start pump was not secured, which allowed for the possibility of it interfering with the fuel quantity transmitter float mechanism, thus providing erroneous cockpit fuel quantity indications to the pilot. The examination also revealed that the low fuel quantity annunciator was inoperative due to separation of the fuel quantity transmitter’s low-level fuel whisker.
The National Transportation Safety Board determined the accident to be a result of improper maintenance resulting in erroneous fuel gauge indications, combined with the pilot’s inadequate fuel management. The investigation also found there were no written company procedures or fuelling records to track fuel loading and time-based fuel consumption.
Survivability
Post-mortem report
The post-mortem examination of the egg collector found multiple blunt force injuries resulting from a fall from a height. The examination identified that there were numerous head, neck, and torso (or trunk) injuries. There was also external evidence of blunt force trauma to the upper and lower limbs, but there were no underlying skeletal injuries. No obvious evidence of fuel was found on the egg collector’s clothing to indicate a fuel leak prior to the accident, but the clothing was not specifically tested for the presence of fuel. Additionally, no bark residue, indicative of tree contact, was identified.
Height of fall
Three studies conducted on patients presenting to an emergency or trauma centre following a fall from height analysed injuries sustained and the height of the fall (Icer and others, 2013, Liu and others, 2008, Nau and others, 2021). The studies found that the overall injury severity was higher with increasing fall height. With increased height of the fall, there was a significantly higher severity of thoracic and pelvic injuries, whereas the severity of head injuries and spinal fractures did not increase with fall height. Life-threatening injuries were more likely the higher the fall height, and falls greater than 18 m were usually fatal (Nau and others, 2021).
In one study, the mean fatal fall height was 6.61 m, noting that the study excluded people who had died before arriving at the hospital. About 30% of people who fell from 10 m or higher died, which was twice the percentage of those who fell from 6–9.9 m and nearly 3 times that of those who fell from 3.1–6 m. Of those fatally injured, 91% sustained head injuries. The study found haemopneumothorax[27] and subarachnoid haemorrhage[28] were the most important factors affecting mortality (Icer and others, 2013). Another study also found severe head injury was a significant prognostic factor for mortality in people who fell from heights of at least 6 m (Liu and others, 2009).
These research findings were consistent with a retrospective study of autopsy reports (Abder-Rhman, Jaber, & Al-Sabaileh, 2018), which found that internal injuries were directly proportional to the height of the fall. Head injury was the most common fatal injury in all heights, chest injuries and skull base fractures were more prevalent in falls from above 3 m, and abdominal injuries were mainly prominent in heights above 9 m.
The Civil Aeromedical Research Institute of the US FAA report Human survivability of extreme impacts in free-fall, analysed factors affecting survivability in individuals who survived falls from heights of up to 84 m (275 ft) (Snyder, 1963). Among other factors, the study found that orientation of the body was important. The initial impacts were feet-first in 10 of the 12 cases of survived falls from over 33 m (100 ft). The impact force was found to be greatly attenuated by bending and flexion of the leg muscles.
Freefall orientation
The sling person’s harness is designed to keep them in an upright position. Keeping the sling person attached during an emergency landing would allow them to remain upright and impact the ground feet first, decreasing the mortality risk. When the sling person is released, they have no means of orientating themselves and are more likely to tumble, increasing the likelihood of landing other than feet first, thereby potentially increasing risk of fatal injury.
Injury assessment
A forensic pathologist assessed the egg collector’s injuries and found that there was evidence of significant head injury due to ground impact. In assessing the height from which the sling person was likely released, the pathologist referenced research showing that higher mortality is found in falls from greater heights and that the threshold for suffering major trauma from a fall from a height is at least 6.1 m (20 ft). Further, that pelvic fractures occur significantly more often if the fall height is at least 6 m, and chest trauma is more common the higher the height of the fall.
Based on the research and the egg collector’s extensive pelvic, spinal, and chest fractures, the forensic pathologist assessed that they likely fell from a height above 5 m.
Egg collector helmet
The egg collector’s helmet was found nearby, and the helmet’s clasp receptacle had fractured.
The instrument issued to Helibrook for picking up and carrying a sling person under an R44 helicopter for crocodile egg collection stipulated that the sling person was to wear a helmet that ‘meets the Australian standard appropriate to the risks encountered during the activity’. The sling person’s helmet had a sticker showing compliance with American National Standard for Industrial Head Protection ANSI/ISEA Z89.12009 Type I Class C. This standard was amended (in 2014) to Z89.1-2014.
The standard stated that Type I helmets were ‘intended to reduce the force of impact resulting from a blow only to the top of the head’. (The Class C (‘conductive’) helmets also provided no electrical protection). In contrast, Type II helmets met additional requirements for lateral impact protection (front, back and sides) and chin strap retention. In this accident, a Type II helmet would not have reduced the severity of the egg collector’s injuries to a survivable level.
Pilot restraint and helmet
The pilot sustained swelling and bleeding on the brain indicative of rapid deceleration and acceleration. Although the pilot was not wearing a helmet, it would likely not have reduced the severity of head injury in this accident as no head impact occurred. The pilot reported always wearing the 4-point restraint and could not recall how they exited the helicopter.
Pilot seat
R44 helicopter seats are designed to crush and absorb impact forces. Under the seat is a stowage area marked with a weight limit and a limitation for storage of soft articles only. The pilot reported that they normally had the following under their seat: lunch, water bottle, satellite phone, first aid kit and a raincoat. A broken headset and other small items were found under the pilot seat and photos from the site showed other items that were removed before ATSB arrived that may also have been stored under the seat.
Impact forces crushed the seat into the storage area, with the seat box and support structure collapsing. Additionally, the fuselage belly pushed upwards after the undercarriage skids exceeded their capability. The floor also pushed up to the level of the collapsed seat pan.
This indicated that the energy absorption capability of the airframe with respect to the seat installation had been exceeded. The seat probably collapsed onto the contents of the stowage compartment and may have contributed to the pilot’s injuries.
Cocaine metabolites
In Australia, cocaine is classed as a ‘Schedule 8 – controlled drug’. Cocaine is a central nervous system stimulant and an illicit drug, unless there is evidence it is used for medical purposes. In a dilute solution, it is used as a topical anaesthetic for limited purposes and is listed as an unrestricted Schedule 8 substance in Northern Territory hospitals. A deputy director at Royal Darwin Hospital advised that cocaine was not stocked in the Emergency Department and was not administered to the pilot at Royal Darwin Hospital. CareFlight NT’s Medical Director advised that their aircraft did not carry topical cocaine.
In the context of aviation safety, detrimental effects of cocaine can occur in the hours immediately after use, and depending on the regularity and dose used, there may also be longer-term effects. Immediate effects of a moderate dose of cocaine on skills performance can include risk-taking, inattentiveness and poor impulse control. During the ‘crash phase’, which lasts 9 hours to 4 days following cocaine use, the user can feel depressed, agitated, irritable, and there can be significant fatigue and lack of energy (Isenschmid, 2002). As the effects of cocaine wear off, the user can suffer fatigue, depression, sleepiness, and inattention (Couper and Logan, 2014).
Cocaine is metabolised in the body to benzoylecgonine and ecgonine methyl ester. Blood concentration of cocaine decreases rapidly and is typically detectable in blood 1–2 days after use. Cocaine metabolites benzoylecgonine and ecgonine methyl ester may be detectable for at least 3–4 days after cocaine use. The presence of benzoylecgonine and other cocaine metabolites in blood in the absence of cocaine usually indicates the cocaine exposure did not occur immediately prior to the blood sampling (Isenschmid, 2002). A toxicological pharmacologist advised the ATSB that it was extremely difficult to correlate blood cocaine concentration with the timing and quantity of exposure to the drug. They also assessed that the pilot’s toxicological results were indicative of exposure to cocaine possibly up to about 4 days prior, but not in the previous 24 hours.
CASR 91.520 detailed that a crew member is unfit for duty if their ability to perform the duty is likely to be impaired because they have used a psychoactive substance such as cocaine. Pilots are required to declare recreational drug use to a designated aviation medical examiner.
Safety analysis
Introduction
From about 0850 on 28 February 2022, the crew of Robinson R44 II helicopter, VH-IDW, were preparing to conduct crocodile egg collection, near King River, Northern Territory. The helicopter was operating under a Civil Aviation Safety Authority (CASA) instrument that authorised the pilot to operate with a person in a harness system (‘sling person’) outside and attached to the helicopter, for the purpose of collecting crocodile eggs. The authorisation was subject to conditions that were intended to mitigate the risks of the operation.
After hearing no communications from the pilot of VH-IDW for more than one hour, another pilot conducting egg collection nearby commenced a search. They found the accident site about 150 m from the first nest they expected VH-IDW’s crew to collect eggs from. The egg collector lay fatally injured on the ground, wearing their harness and attached to one end of the sling. The attachment rings at the other end of the sling were not connected to the helicopter, which had collided with the ground upright, 44 m from the egg collector, and was substantially damaged. The pilot sustained serious injuries.
There were no witnesses to the accident and the accident pilot had no recollection of the accident and limited recollection of the hours leading up to it. No recorded data to accurately determine the accident sequence, including the time of the accident, was recoverable.
There was no fuel present in the helicopter’s auxiliary tank and a very small quantity in the main tank. Assessment of the helicopter indicated that the engine was stopped before the helicopter impacted the ground. Additionally, there was no evidence of failure of the harness, sling, attachments or the hooks system. There was also no evidence of failure or defects to the airframe or the helicopter’s systems likely to have contributed to the accident.
This analysis will discuss:
fuel uplift
the pilot’s awareness of the helicopter’s fuel state
potential reasons for the in-flight engine stoppage
the circumstances relating to the release of the sling person and the helicopter’s collision with terrain.
The influence of the helicopter operator’s safety management system and the Civil Aviation Safety Authority’s (CASA’s) process for issuing authorisation instruments will also be analysed. Finally, the potential contribution of the helicopter’s state of airworthiness, presence of cocaine metabolites in the pilot’s toxicology results and lack of emergency location transmitter fitted to the helicopter will also be considered.
Fuel uplift
After reportedly being filled with fuel, the helicopter departed from the operator’s hangar at Noonamah on the outskirts of Darwin at about 0703 in company with 2 other R44 helicopters. Fuel receipts showed that the Noonamah fuel tank contained only blue‑coloured 100 low lead (LL) Avgas fuel and there was no record of the quantity of fuel uplifted to VH-IDW at Noonamah on the accident morning. An in-flight photo taken en route to Mount Borradaile showed the chronometer reading 45 minutes, which the pilot reported usually setting to zero after refuelling.
A subsequent report that VH-IDW was filled the evening prior to the accident and not on the accident morning, suggested that VH-IDW departed with less than full fuel (151–153 L usable). However, the in-flight photo showed the gauges reading slightly below 3/4, consistent with the helicopter having departed Noonamah at or near full, based on the reported fuel flow rate of about 65 L/h.
Based on flight data, witness accounts and evidence from the in-flight photo, the 3 helicopters probably arrived at the en-route fuel depot at Mount Borradaile at around 0816. The accident pilot reported that they always left Mount Borradaile with full fuel tanks and their intention had been to refuel there. However, they were unable to confidently recall the specific fuelling activities at Mount Borradaile or events thereafter.
There were consistent recollections from others present at Mount Borradaile that VH-IDW was the first helicopter to arrive and that it did not have a fuel drum pump on board to transfer fuel from the drum stock. However, there were also differing recollections of the order in which the R44s were refuelled, with each helicopter being repositioned in turn close to the drums and the entire activity being undertaken without shutting any of the aircraft down. Two people reported seeing the accident pilot pumping fuel, including into VH-IDW. However, in a submission following review of the draft report, one of those reported not having seen anyone fuel VH-IDW. One other person reported assisting the pilot to pump fuel. However, that person’s recollection subsequently changed to having observed the egg collector partially fuelling VH-IDW before taking over to finish the fuelling themselves.
In the approximately 14 minutes the helicopters were at Mount Borradaile, there was probably sufficient time to refuel 3 helicopters given the number of people available to assist. Two witnesses reported that the egg collector was flying VH-IDW, from the right seat, when it departed Mount Borradaile, and that the accident pilot removed the dual controls after arriving at King River. However, the accident pilot and another egg collector reported that the accident pilot had flown VH-IDW from Mount Borradaile, having removed the dual controls there.
The ATSB’s assessment, based on the consistent accounts of the first 2 witnesses and recorded GPS data transmitted to a server from the egg collector’s phone indicating they were using an electronic flight bag application to navigate between Mount Borradaile and King River, was that it was more likely that the egg collector flew VH-IDW from Mount Borradaile to King River.
The person who prepared the 2 fuel drums for the R44 crews on the accident morning at Mount Borradaile had a detailed recollection of which drums were used and subsequently obtained fuel samples from those drums for ATSB testing. The samples were confirmed as green‑coloured 100/130 fuel in accordance with the relevant specifications and the delivered batch test data.
The first person to arrive at the accident site, reported that there was a fuel smell but later assessed that may have been from a leaking jerry can stored behind the pilot’s seat. The first emergency responder on site reported the absence of a fuel smell, but noted leaking hydraulic fluid that created a sheen on the water. The Helibrook chief pilot also reported that there was no fuel smell when they arrived. As the helicopter wreckage was in a swamp, with water slowly running downstream, it was possible for fuel to also drain away, although no one observed that occurring. There were also varying reports that people who attended the site after the accident looked in one or both fuel tanks and detected fuel, but no one attempted to measure the quantity.
When ATSB investigators arrived at the accident site 2 days after the accident, there was no fuel present in the auxiliary tank and only a small quantity of fuel in the main fuel tank. Although it was not possible to accurately measure the quantity in the main fuel tank on‑site, it was assessed by the ATSB investigators to be significantly less than the documented unusable quantity of 4 L. Recognising that the worst‑case helicopter orientation is used to arrive at that unusable fuel quantity, it is possible to consume some of the published 4 L in‑flight. However, it was considered unlikely that the small remaining quantity observed by the ATSB on‑site would have sustained the engine. As such, following the ground collision some fuel was either removed from the helicopter or was able to drain away.
Examination of the helicopter identified that it was possible for fuel to drain under gravity from the tanks through the fuel system and out via either a fractured fitting between the fuel flow transducer and flow divider, or through the drain at the gascolator. However, the loose organic black soil from the accident site that filled the fractured transducer fitting would likely have been flushed out if fuel had drained through that route. There was also no fuel staining on the cowls, but this may have been due to water ingress into the cowls at the accident site. Images taken of the site 4 months after the accident showed no evidence of vegetation dieback that would be indicative of significant fuel leakage, however over 200 mm of rain had fallen in the intervening period.
The helicopter manufacturer assessed that the deformation of the fuel tanks was consistent with a lower fuel quantity, but was unable to distinguish between some or no usable fuel remaining, or between impact damage and possible bulging due to internal contents. However, the degree of tank deformation indicated that the helicopter was not filled with any significant amount of fuel at Mount Borradaile unless the accident occurred at about the time the helicopter was located. This was considered unlikely because the accident occurred between the clearing and the first target nest in the direction of travel that morning. Other than the egg collector’s phone briefly contacting a cell tower at 0858, there was no evidence the crew planned to go anywhere other than the 3 nests they had been allocated to collect, and no eggs had been collected. There was no communication between the cell tower and the pilot’s phone at that time.
Scientific testing of the fuel drained from VH-IDW after the accident found that it was 100 LL Avgas and likely contained no more than 1% 100/130 fuel, consistent with residue from previous fuelling. This physical evidence opposed any significant quantity of 100/130 fuel being added to the tank at Mount Borradaile. Although it was later reported that it was possible for other drums at Mount Borradaile containing 100 LL to have been used, the distinct drum markings and reported general usage of the fuel location made that unlikely.
The potential effect of interference with the site was considered in relation to the removal of the jerry cans and the fuel testing results. The only plausible scenario that permitted both refuelling at Mount Borradaile to occur and the sole presence of 100 LL when chemically tested was if 40 L of 100 LL fuel was poured from the jerry cans into VH-IDW after the accident and then subsequently largely leaked away.
While it was possible that the addition of 40 L of 100 LL from the jerry cans could produce the attained test results, there was no evidence that occurred. Conversely, those on‑site reported that one of the jerry cans was damaged on impact and fuel from the jerry cans out of VH-IDW was used to fuel one of the other helicopters before departing the accident site. This was consistent with reports of empty jerry cans being used at Mount Borradaile to transfer fuel from a drum to a helicopter on the return trip. Additionally, the lack of fuel smell, cowl staining and soil lodged in the fractured transducer fitting also indicated that 40 L of fuel was not poured through the system.
Considering the relatively greater strength of the technical evidence, the ATSB concluded that the helicopter was probably not refuelled at Mount Borradaile prior to the commencement of the egg collecting activity.
Detection of low fuel state
The sources of information for the pilot regarding the helicopter’s fuel state were the chronometer, fuel totaliser, fuel log, fuel gauges and low fuel warning system.
The pilot’s normal practice, consistent with the in-flight photo was to reset the chronometer to zero following refuelling. The chronometer did not store data and therefore its reading at the time of accident could not be determined. The pilot reported that they did not use the totaliser, which was not visible in the in-flight photo. Further, there were no records of fuel uplifted to VH-IDW for the accident day.
When tested, the main tank indication overread within a needle-width at empty, a quarter and half full. The auxiliary tank gauge indicated very close to the actual fuel level. The placard below the main fuel tank gauge, from the last fuel calibration, indicated the main tank gauge would significantly underread. Therefore, had the pilot been relying on the calibration placard’s quantity to interpret the gauges, there would have been less fuel in the main tank than expected, other than when full or empty. However, based on the in-flight photo showing the fuel gauges, and testing of the gauge senders and gauges, the gauges would likely have been reasonably accurate.
The calibration placard also stated the low fuel warning light would illuminate with 20 L fuel total remaining and the pilot recalled that it would illuminate with 18 L remaining. However, according to VH-IDW’s Pilot’s Operating Handbook, the low fuel warning light would illuminate with 11 L of usable fuel remaining, which would be 14 L total. It is therefore likely that, if the light illuminated in flight, the pilot would think there was more fuel remaining than the POH indicated. The accident pilot also reported that their normal practice was to depart Mount Borradaile with full fuel. This expectation may have influenced the degree to which the pilot focused on the fuel quantity.
The low fuel warning system was found to be functional. However, it is possible that, if the low fuel light and/or fuel gauges were indicating low fuel, the accident pilot may have dismissed these cues as they would not have been consistent with their expectation. Additionally, had the low fuel light illuminated, the pilot may have thought there was more fuel remaining than actual.
A previous ATSB investigation into a Robinson R22 accident that occurred during mustering operations, found that the nature of the operation potentially diverted the pilot’s attention away from monitoring the helicopter’s fuel state. This resulted in probable fuel exhaustion and stoppage of the engine in flight. This potential also existed in conducting slinging operations, as the pilot would have had their head out the door, looking down at the sling person, and not at the instrument panel or gauges. This limitation of monitoring gauges was included in the Helibrook operations manual and suggested pilots conducting low-level aerial work operations also monitor elapsed flight time. However, had the chronometer been reset to zero at Mount Borradaile but the helicopter not refuelled, this would have provided an erroneous indication of time since refuelling.
Had the pilot detected a low fuel situation, there were 2 jerry cans of 100 LL fuel in VH-IDW that could be used for refuelling and multiple landing sites were available. Ultimately, while indications of the in-flight fuel state should have been available to the pilot, the pilot may have not observed them, dismissed them as erroneous or misinterpreted them. In any case, it is likely that the pilot did not recognise the helicopter’s fuel state.
In assessing whether the pilot’s experience as a helicopter pilot and in slinging operations would mitigate the risk of fuel exhaustion, the ATSB reviewed fuel exhaustion occurrences in the 10-year period 2011–2020. The median total experience of pilots involved in fuel exhaustion occurrences reported to the ATSB in that period was 1,227 hours. This illustrates that experience alone does not mitigate fuel exhaustion.
In-flight event assessment
The ATSB analysed what in-flight event occurred that led to the egg collector dropping their equipment, the pilot releasing them, and the subsequent helicopter collision with terrain. The orientation of the accident trail was consistent with the route between the clearing and the nest most likely to be collected first. There was no evidence of snagging of the sling line or egg collector that led the pilot to release them. There was also no evidence of in-flight breakup or damage to the helicopter airframe due to failure, bird strike, or consistent with a manoeuvring error or mishandling.
Significantly, there was physical evidence that the engine was stationary when the helicopter impacted the ground, and no evidence that supported engine rotation was identified. Based on advice from the helicopter manufacturer, the ATSB assessed whether the engine had stopped in flight or because of the main rotor blade striking the tree while the engine was producing low power. The damage to the main rotor blade, including one broken pitch link, was consistent with a tree strike in a low rotor energy state. The diameter of the branches struck on the first 2 strikes was assessed as too small to stop the engine. The last tree strike was more substantial but occurred below the main rotor blade height, indicating the helicopter impacted the ground prior to that strike. On balance it was therefore considered likely that the engine stopped in flight.
Reason for engine stoppage
Pilot action
The ATSB assessed the possibility of inadvertent pilot-induced engine stoppage in the context of the pilot’s logged total helicopter flight experience of about 2,500 hours and more than 300 hours of sling time. Robinson advised that there had been several accidents in which a pilot had inadvertently induced an engine stoppage by rolling off the throttle too fast. This had occurred in flight training when simulating an engine failure and as an incorrect response to abnormal situations such as a sudden change in engine RPM or discrepancy between engine and rotor RPM.
It was considered very unlikely that the pilot would have simulated an engine failure at any stage during the accident flight. Although it could not be determined whether there was another situation that led to the pilot quickly rolling off the throttle, this would be a highly unlikely response of an experienced pilot, while conducting human external cargo (HEC) operations.
Aircraft, engine and fuel system examinations
The ATSB conducted extensive airframe and component examinations. Independent experts were engaged to conduct engine and fuel system examinations, overseen by the ATSB and other involved parties. The results were also analysed by manufacturers of the helicopter and engine, and other specialists. There was no evidence of a defect that could have led to sudden stoppage of the engine, of any critical component of the engine, fuel, or other helicopter system. Examination of the engine and fuel system found:
no evidence of any issue with air intake to the engine or the exhaust system
low static compression in one cylinder, but the actual compression was probably higher when the engine was running and warm, which was unlikely to have resulted in sudden in-flight complete or substantial power loss
several valve clearances were out of service limits
no evidence of any issue with the spark plugs, ignition leads or magnetos
no fuel remaining in the system other than the main fuel tank, no evidence of fuel contamination with debris, water, or wrong fuel, no defects in the fuel system and no condition likely to prevent usable fuel reaching the engine.
The out‑of‑limit valve clearances and low cylinder compression probably reduced the power that the engine was able to produce. However, the accident was not consistent with insufficient power available to lift the sling person, as the maximum power required would have occurred during the lift and before forward speed (consistent with the accident trail) was achieved. The ATSB assessed VH-IDW for all the possible reasons for an engine problem listed by the engine and helicopter manufacturer. The aircraft, engine and fuel system examinations did not identify any failure or condition, other than an absence of fuel throughout the system, that would likely result in sudden complete or substantial engine power loss.
Fuel exhaustion
The helicopter had not been shut down between when it was started before 0700 and last seen at a clearing near King River at about 0855. No recorded data was available to indicate the helicopter’s movements after 0900, including at the time of accident. However, the egg collector’s phone was momentarily in range of the nearest phone tower at 0858 and the accident pilot’s phone was not. As mobile phone reception was only in range when about 300 ft above the accident site, this may indicate that the egg collector was briefly airborne in the helicopter at that time.
As described above, the accident occurred between the clearing and VH-IDW’s first target nest, and no eggs had been collected. Additionally, no communication had been made with VH-IDW since about 0900, and it was considered unusual for the crew not to communicate for over an hour.
The operator reported VH-IDW’s normal fuel flow was 65–70 L/h, equating to a fuel endurance between 2 hours 31 minutes and 2 hours 42 minutes. Had the helicopter not been refuelled since 0658 at Noonamah, the helicopter would have exhausted usable fuel between 0929 and 0940. Furthermore, if the helicopter had been refuelled the previous evening and then travelled for about 23 minutes to Noonamah, and was not fuelled prior to the start of the accident day, fuel exhaustion was possible from 0904. Low cylinder compression evident in the No. 6 cylinder at engine examination, and high power settings, as evident in the in-flight photo, increase fuel consumption. Fuel exhaustion was therefore possible earlier than 0929. This was consistent with the search pilot’s estimation that the accident occurred at about 0922, when they were on the ground and out of communication range, and other crew heard a static radio transmission that may have been from VH-IDW.
The helicopter’s hour meter read 2070.05 at the accident site and the maintenance release recorded 2067.6 at the end of the previous day. This indicated the helicopter had a flight time of 2.45 hours (not including time on the ground), which would also support fuel exhaustion. However, this was considered unreliable evidence as the pilot reported that the hour meter was never running when they operated VH-IDW, in which case the maintenance release did not reflect actual hours flown.
In summary, considering the:
likely lack of fuel on site, including in the helicopter tanks
elapsed time since last probable refuelling
timeframe in which the accident likely occurred
the absence of any fault with the helicopter likely to result in sudden or substantial power loss
fuel exhaustion was assessed as the probable reason for engine stoppage.
Release of sling person and helicopter terrain impact
There was no evidence of a failure of the hooks system or sling equipment. The pilot reported that they always checked both quick release systems were functional before slinging. Had the experienced egg collector not attached themselves correctly, it was unlikely the pilot would have been able to lift them into the air attached to the helicopter and traverse above trees before they were released. By design and certification, inadvertent release of the hooks by the pilot was extremely improbable. Furthermore, inadvertent release of the egg collector would not have resulted in the subsequent helicopter ground collision without an additional failure/malfunction or mishandling. Therefore, the pilot almost certainly released the sling person, consistent with their stated procedure in the event of an engine failure or malfunction in the vicinity of trees.
Due to a lack of recorded data or recollection from the pilot, an assessment could not be made of the height and speed of the helicopter when the engine stopped or the egg collector was released. The trees between where the helicopter probably took off and the vicinity of the accident site were between 12–15 m tall, with taller trees up to 18 m tall closer to the crocodile nest site. The pilot’s reported procedure was to remain within about 5 m above the vegetation and therefore, if following their stated practice, the egg collector was likely about 20 m above the ground when the power loss occurred. Considering the length of the sling line, that would have positioned the helicopter about 50 m (164 ft) above the ground.
To estimate the height from which the egg collector was released, their injuries were assessed by a forensic pathologist using survivability research into falls from heights. Based on the injuries sustained, the pathologist assessed that the egg collector likely fell from at least 5 m above the ground. Additional research reviewed by the ATSB that considered how specific injuries varied with height indicated a likelihood that the egg collector was released from above 9 m, from which most falls are fatal.
Based on the pilot’s reported normal practice to minimise height and speed while slinging, the helicopter was likely operating within the ‘avoid’ area of the helicopter’s height-velocity graph. In that area, the combination of height and airspeed was such that a pilot may have been unable to complete an autorotation landing without damage. This was consistent with the low rotor energy and crushing of the fuselage evident in the damage sustained by VH-IDW.
The helicopter’s vertical descent through at least the last 8 m (24 ft), which was the height of the tree that the main rotor blade struck 3 times, was consistent with an attempt to avoid the obstacles ahead (due to densely growing tall trees) relative to the direction of travel.
Helibrook safety management
Helibrook had introduced a CASA-accepted safety management system (SMS) in conjunction with CASA’s approval of the Helibrook chief pilot. This included purchase of a third‑party produced SMS manual and assigning the operations manager to also perform the safety manager role. The SMS manual stated that through the SMS, Helibrook would identify hazards and risks, with the goals of minimising risk, maintaining the health of stakeholders, and continually improving safety.
An assessment of the operator’s SMS following the accident quickly identified that in the 2 years since its approval, Helibrook had not implemented the system described in the SMS manual. Time or resources had not been allocated to safety management tasks, and the safety manager’s priority had been to fulfill their other role as operations manager. There was no evidence of a maturing safety culture, in which effective hazard identification enabled actions to proactively manage risks and prevent accidents. No formal, documented risk assessment had been conducted for any of Helibrook’s approved activities, including human external cargo (HEC) operations. As an operator conducting a specialised high-risk activity, application of the SMS would have assisted the identification of hazards and risk controls to reduce the risk of harm to operating crew.
CASA’s approval to conduct HEC operations required the pilot and egg collector to assess that the risk of heat illness and crocodile attack outweighed the risks of slinging. A structured risk process would have provided a means for this assessment to be made as well as identifying occasions when slinging was unacceptably risky. The same process should also have identified mitigations to reduce the:
likelihood of an emergency event occurring, such as:
good maintenance practices and adherence to operating limitations to ensure ongoing helicopter airworthiness
ensuring that required pilot briefing and training in HEC operations were conducted, including fuel management
consequences of an in-flight emergency, such as height and speed limits for carrying the sling person, and fitting the helicopter with an emergency locator transmitter.
In not using their SMS, Helibrook did not identify the risks associated with conducting human external cargo operations, particularly the carriage of the egg collectors at non‑survivable fall heights, and ensure they were adequately managed.
The Civil Aviation Safety Authority’s approval process
Approval process
Picking up and carrying a person outside a helicopter was not permitted without specific authorisation. CASA could only grant such an authorisation, if doing so would be unlikely to have an adverse effect on safety. To ensure safety was preserved, CASA could impose conditions set out in an authorisation instrument.
Guidance was available for the administrative side of processing a request for an authorisation. However, there were no guidance or tools for conducting the safety assessment to determine whether an authorisation and its conditions assured the preservation of safety. Flight operations considerations for approving an aerial work activity were detailed in the Air Operator’s Certificate (AOC) Handbook, but this did not include the management of risk. The AOC handbook also contained safety management and risk assessment guidance for assessing an AOC holder's SMS, but the CASA delegates contacted by the ATSB as part of this investigation did not consider this relevant to the instrument approval process.
The first approval instrument to conduct HEC operations for the purpose of crocodile egg collection was reported to have been issued in 2007, and subsequently reissued generally on an annual basis. CASA was unable to locate records of instruments issued before 2010, any assessment as to whether the authorisation was likely to adversely affect safety, or how the imposed conditions mitigated the risks. The first instrument obtained by the ATSB was for 2010 and listed 20 conditions. These included a requirement that hooks were fitted to the helicopter under an appropriate design approval and limitations to the height, speed and distance the sling person could be carried.
The CASA delegates who issued authorisation instruments for R44 HEC for crocodile egg collection from 2013–2021 incorrectly assumed a risk assessment had been performed when the first instrument was issued. The delegates also assumed previous approvals meant that the risks of HEC operations had been assessed as acceptable by CASA, and that the conditions included in the instrument mitigated the risks. However, none of the delegates had sighted a risk assessment for the activity, nor did they conduct one, including when changing or removing instrument conditions. Additionally, although the instrument only permitted operators to conduct HEC if there was an overall safety advantage in reducing the risk of crocodile attack and heat illness, CASA did not ensure that the operators had a process for assessing the relative risks.
In the absence of a formal risk assessment process, delegates based their approval of the activity and the imposed conditions on the advice of CASA flight operations and airworthiness inspectors, and a reasonableness test. Additionally, delegates considered the instruments were reissues of an existing approval even when removing or amending conditions. Therefore, if there were no changes to procedures and no accidents, they assessed that there was no reason not to issue an authorisation, as the level of safety was considered not to have changed.
A draft HEC in piston engine rotorcraft risk management plan (RMP) using a CASA general aviation template was prepared by CASA Flight Standards Branch personnel and presented to CASA executive in 2013. The RMP and associated template was a formal risk assessment tool. The RMP assessed that HEC operations in single engine piston (R44) and turbine helicopters was an unacceptable risk without mitigations to improve helicopter reliability, and speed, height and duration limitations for carrying the HEC.
The RMP formed the basis of CASA’s proposed standard to cease issuing approvals for HEC with the R44 and to require a single engine turbine helicopter with a usage monitoring system. This was due to the associated higher risk of in-flight power loss and additional failure modes of an R44. The turbine engine requirement aligned with US and European regulations and was to be included as an amendment to Civil Aviation Order 29.6. That amendment was abandoned in 2016, due to planned implementation in 2018 of the same ruleset incorporated in Civil Aviation Safety Regulations Part 138. However, regulatory change took longer than anticipated, and Part 138 was implemented in December 2021. None of the delegates involved in approving instruments after 2013 reported having seen the RMP.
As the instrument conditions were described as risk mitigations, a formal risk assessment would have enabled delegates to quantify the change in overall risk associated with changes to, or removal of, conditions. Without a formal risk management process, CASA delegates were unable to show in a structured way that an authorisation did not adversely affect safety or that the conditions included in an authorisation were sufficient to achieve the required level of safety.
Influence on human external cargo risks
Once the hooks met the required certification standard, failure of the hooks was extremely improbable. As a result, CASA approved amendments to the rotorcraft flight manual supplement associated with the dual hooks. These included the removal of limits for the height and distance a sling person could be carried and an increase of the maximum slinging speed to 60 kt. However, this did not consider circumstances that could result in release of the sling person, other than failure of the hooks.
CASA delegates then removed the HEC limitations from CASA’s instrument conditions. It is unclear why these conditions were removed. However, as a formal risk assessment was not performed it was not identified that there were other failure conditions likely to result in release of the sling person and that the removal of height and speed limits for carrying the sling person significantly increased the overall risk.
Falls from greater than 5 m above the ground are more likely to result in a fatality. CASA’s removal of those limitations meant that an operator could both operate within an authorisation instrument’s conditions and permit an avoidable fatal outcome for a sling person in the event of an emergency release, such as occurred during this accident.
Continued unmitigated operational risk
As CASA delegates had not formally assessed the operational risk of using an R44 helicopter they continued to approve R44 HEC for crocodile egg collection without assurance that aviation safety was preserved. Although CASA’s RMP assessed that a single turbine engine helicopter with a usage monitoring system had a higher reliability and less likelihood of engine failure than an R44 helicopter, it did not consider or compare the hazard of fuel exhaustion.
Having formally assessed the risks for the RMP in 2013, the following year, CASA Flight Standards Branch personnel engaged with operators who conducted HEC for crocodile egg collection and advised of CASA’s intent to require a turbine helicopter with a usage monitoring system for improved helicopter reliability. CASA personnel then drafted the relevant legislation and engaged with the industry before it was finalised. Although operators had been notified and engaged during the rulemaking process, shortly prior to commencement of the regulations in 2021, a CASA delegate issued Helibrook with a 3-year instrument approving continued use of an R44 helicopter for human slinging operations. This resulted in continuation of what CASA had assessed as an unacceptable ongoing risk.
There was insufficient data available of helicopter fuel exhaustion accidents to indicate an increased risk in piston engine helicopters compared with turbine engine helicopters. There was also insufficient evidence from which to assess the difference in outcome between an autorotation in a single engine turbine helicopter and in an R44. Single engine turbine helicopters, with a higher inertia rotor than the R44, may provide more opportunity to place the sling person on the ground, as occurred in a Bell 407 accident in the US in 2022, and reduce the consequences for the pilot in an autorotative landing. However, operating in any helicopter's height-velocity avoid area does not ensure a safe landing can be made.
Without adequate height and speed limitations to protect the sling person, there is no evidence that the use of a single turbine engine helicopter would have altered the outcome in this accident.
Engine defects
The low compression in one cylinder and valve clearances out of service limits increased the likelihood that the engine's maximum power output was reduced. Although the engine was derated, to counter the reduction in performance at higher density altitudes, the defects increased the risk of having insufficient performance for the helicopter to hover out of ground effect, essential to conduct slinging operations.
The higher-than normal fuel flow for slinging operations was unlikely to have affected the pilot’s assessment of fuel endurance. This was because the pilot had conducted slinging in VH-IDW the day prior to the accident and the fuel flow would unlikely have changed since then. The in-flight photo taken on the accident morning showed the helicopter operating above the manifold pressure limit at the time, which may have been symptomatic of reduced engine performance.
The approval to conduct HEC operations required that the engine was capable of making maximum rated power and able to hover out of ground effect 3,000 ft above the ground. Poor engine condition increased the likelihood of insufficient power available to conduct safe slinging operations and of an in-flight failure. However, there was no evidence of any failure or condition that would have suddenly stopped or significantly reduced engine power.
Helicopter hours overrun
Accurate recording of time in service is required to ensure helicopter components are inspected, overhauled or replaced within life limits. Exceeding the life limits increases the probability of component failure and renders the helicopter unairworthy.
VH-IDW was to be maintained in accordance with the airframe and engine manufacturers’ maintenance schedule, which required a periodic inspection every 100 hours or 12 months, whichever occurred sooner, and was subject to overhaul at 2,200 hours or 12 years, whichever occurred first. Based on a review of VH-IDW’s maintenance releases, at the periodic inspections, the helicopter’s hour meter matched the time in service recorded on the maintenance release.
Based on the hour meter reading at the accident site, VH-IDW had about 192 hours until overhaul. The ATSB found the hour meter connected, but one of the 2 connections was only finger tight, consistent with having been connected by hand. Additionally, the hour meter had almost certainly been disconnected for periods, resulting in under-recording of the hours in operation. Based on a comparison of the hours recorded on VH-IDW’s maintenance releases with hours recorded in spreadsheets and on the pilot’s phone, it was likely the helicopter had been overrunning the 100-hour maintenance intervals and had exceeded its overhaul life. This was also supported by a CASA airworthiness inspector’s review of maintenance records, which identified the engine-driven fuel pump being replaced at decreasing recorded hourly intervals, as VH-IDW approached its end of overhaul life and while being operated by Helibrook.
In-use hours for the hooks were independent from total helicopter hours but were also not being recorded. Additionally, one hook was overdue for overhaul based on calendar time and the hooks had not been maintained as required, but there was no evidence these had failed.
Although overrunning maintenance, inspection and overhaul periods increased the likelihood of component failure, there was no evidence of an engine, airframe or hook component failure that resulted in the engine stoppage, helicopter accident or increased severity of injuries or damage. Despite that, while operating in the height-velocity avoid area, a successful autorotation was not guaranteed. Therefore, high reliability of the helicopter and systems was necessary to mitigate the risks to the pilot and the sling person. In stopping the hour meter and exceeding maintenance, inspection and overhaul limits, the operator increased the likelihood of a catastrophic component failure of the helicopter. This posed an unnecessary increase in risk for the pilot and particularly sling crew conducting HEC operations.
Cocaine metabolites
Cocaine is an illicit drug and can have deleterious effects on pilot performance. Possible effects include risk-taking, inattentiveness and poor impulse control. Although the pilot reported that they did not use cocaine, very low levels of cocaine metabolites were found in the pilot’s toxicology results.
On the basis that the metabolites indicate exposure to cocaine, the detected levels indicated the pilot had not been exposed to cocaine within the previous 24 hours and may not have been affected by cocaine on the accident day. There was insufficient evidence to enable an assessment of whether the drug contributed to the development of the accident. However, the indication of exposure to cocaine is highlighted, as the effects of cocaine and post-cocaine exposure clearly increase risk to aviation activities. The post-cocaine exposure effects can include fatigue, depression and inattention.
Emergency locator transmitter
The helicopter's emergency locator transmitter was not mounted and did not activate in the accident impact. Although the actual time of the accident could not be established, there is a high likelihood that it was a significant time before the helicopter was located. Therefore, had the emergency locator transmitter been fitted and activated on impact, emergency medical care may have arrived sooner.
Immediate notification to rescue medical services can have a significant effect on the outcome for occupants of a serious aircraft accident. Although prompt medical attention would not have altered the outcome for the egg collector, the pilot’s condition likely worsened over time since the accident. The actions of the individual to search for VH‑IDW and alert emergency services contributed to the pilot’s survival, but more timely initiation of medical assistance would have reduced the risks of exacerbating the pilot’s injuries and deterioration of their condition.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’. In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
Safety issues are highlighted in bold to emphasise their importance. A safety issue is a safety factor that (a) can reasonably be regarded as having the potential to adversely affect the safety of future operations, and (b) is a characteristic of an organisation or a system, rather than a characteristic of a specific individual, or characteristic of an operating environment at a specific point in time.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
At the time this report was published there were ongoing police investigations concerning the status of evidence at the accident site. Acknowledging this, the following findings are made with respect to the collision with terrain involving Robinson R44 II, VH-IDW, at King River, Northern Territory, on 28 February 2022 on the evidence obtained by the ATSB.
Contributing factors
Following likely not refuelling at Mount Borradaile, the pilot did not identify the reducing fuel state before the helicopter engine stopped, probably due to fuel exhaustion.
During the autorotation, the pilot released the egg collector above a likely survivable height, resulting in their fatal injuries.
The pilot continued the autorotation to the ground but there was insufficient main rotor energy to cushion the landing, resulting in serious injuries to the pilot and substantial damage to the helicopter.
Helibrook’s approved safety management system was not being used to systematically identify and manage operational hazards. As a result, risks associated with conducting human external cargo operations such as carriage of the egg collector above a survivable fall height were not adequately addressed. (Safety issue)
The Civil Aviation Safety Authority (CASA) did not have an effective process for assuring an authorisation would be unlikely to have an adverse effect on safety. As a result, CASA delegates did not use the available structured risk management process to identify and assess the risks, ensure appropriate and adequate mitigations were included as conditions of the approval, or assess the effects of changes on the overall risk. (Safety issue)
CASA's lack of effective process for assuring an authorisation would be unlikely to have an adverse effect on safety resulted in the removal of height, speed, and exposure limits, which permitted carriage of the egg collector above a survivable fall height.
The following factors were considered important to include in the report for the purpose of increasing awareness and enhancing safety, but there was insufficient evidence to show they contributed to the accident or severity of the consequences, or to another contributing safety factor.
Other factors that increased risk
CASA's lack of effective process for assuring an authorisation would not have an adverse effect on safety resulted in the continued operation of piston engine helicopters for human sling operations without adequate mitigations and the issue of a 3-year instrument to Helibrook shortly prior to the commencement of improved regulations, which would require a turbine engine helicopter for human slinging operations.
Several engine defects were present at the time of the accident. Although there was no defect likely to result in sudden power loss, these factors likely affected the engine maximum power output and fuel consumption.
Helibrook had likely overrun the helicopter's maintenance, inspection and overhaul periods, which increased the likelihood of the helicopter experiencing a technical failure or malfunction.
The presence of cocaine metabolites in the pilot’s blood sample indicated the pilot had been exposed to cocaine within the previous few days, increasing the likelihood of fatigue, depression and inattention.
The helicopter's emergency locator transmitter had been removed from its mount prior to the accident. Therefore, it could not activate automatically, which likely delayed the emergency response.
Safety issues and actions
Central to the ATSB’s investigation of transport safety matters is the early identification of safety issues. The ATSB expects relevant organisations will address all safety issues an investigation identifies.
Depending on the level of risk of a safety issue, the extent of corrective action taken by the relevant organisation(s), or the desirability of directing a broad safety message to the aviation industry, the ATSB may issue a formal safety recommendation or safety advisory notice as part of the final report.
All of the directly involved parties were provided with a draft report and invited to provide submissions. As part of that process, each organisation was asked to communicate what safety actions, if any, they had carried out or were planning to carry out in relation to each safety issue relevant to their organisation.
Descriptions of each safety issue, and any associated safety recommendations, are detailed below. Click the link to read the full safety issue description, including the issue status and any safety action/s taken. Safety issues and actions are updated on this website when safety issue owners provide further information concerning the implementation of safety action.
Safety issue description: The Civil Aviation Safety Authority (CASA) did not have an effective process for assuring an authorisation would be unlikely to have an adverse effect on safety. As a result, CASA delegates did not use the available structured risk management process to identify and assess the risks, ensure appropriate and adequate mitigations were included as conditions of the approval, or assess the effects of changes on the overall risk.
Safety issue description: Helibrook’s approved safety management system was not being used to systematically identify and manage operational hazards. As a result, risks associated with conducting human external cargo operations such as carriage of the egg collector above a survivable fall height were not adequately addressed.
Glossary
AC
Advisory circular
AEB
Airworthiness and Engineering Branch
AMSA
Australian Maritime Safety Authority
AOC
Air Operator’s Certificate
AWB
Airworthiness bulletin
BHP
Brake horsepower
BQRS
Back-up quick release system
CAO
Civil Aviation Order
CAR
Civil Aviation Regulations
CASA
Civil Aviation Safety Authority
CASR
Civil Aviation Safety Regulations
CST
Central Standard Time
DAMP
Drug and alcohol management plan
DAS
Director of Aviation Safety
DOI
(US) Department of the Interior
EASA
European Union Aviation Safety Agency
ELT
Emergency locator transmitter
EMI
Electromagnetic interference
EO
Engineering order
EPIRB
Emergency position indicating radio beacon
FAA
(US) Federal Aviation Administration
FAR
(US) Federal Aviation Regulations
FCU
Fuel control unit
FMEA
Failure modes and effects analysis
FPRV
Fuel pressure relief valve
HAAMC
Head of aircraft airworthiness and maintenance control
HEC
Human external cargo
HF
High frequency
H/V
Height-velocity
IAS
Indicated airspeed
ICAO
International Civil Aviation Organization
KIAS
Knots indicated airspeed
LL
Low lead
MOS
Manual of standards
MR
Maintenance release
NT
Northern Territory
NTSB
(US) National Transportation Safety Board
POH
Pilot’s operating handbook
PQRS
Primary quick release system
RFMS
Rotorcraft flight manual supplement
RHC
Robinson Helicopter Company
RMP
Risk management plan
RPM
Revolutions per minute
SMS
Safety management system
SN
Safety Notice
SOP
Standard operating procedure
SPO
Specialised operation
STC
Supplemental type certificate
SWMS
Safe work method statement
TBO
Time between overhaul
UHF
Ultra high frequency
US
United States
USG
US gallons
VHF
Very high frequency
WHNT
Wild Harvest Northern Territory
Sources and submissions
Sources of information
The sources of information during the investigation included the:
pilot of the accident flight
other pilots who conducted flights for the operator
other crews conducting egg collecting
helicopter maintainer
helicopter operator and chief pilot
Northern Territory Police Fire and Emergency Service
Abder-Rhman, H., Jaber, M.S., & Al-Sabaileh, S.S. (2018). Injuries sustained in falling fatalities in relation to different distances of falls. Journal of Forensic and Legal Medicine 54:69-73.
Couper, F.J. and Logan, B.K. (2014 revision). Drugs and Human Performance Facts Sheets. Technical Report DOT HS 809 725, National Highway Traffic Safety Administration (NHTSA), Washington DC.
Department of Defence, Defence Science and Technology Group (2022). Fuel analysis for ATSB Investigation AO-2022-009 involving Robinson R44, VH-IDW. DSTG-CR-2022-0060.
Department of the Interior (2010). Helicopter short-haul handbook. US DOI 351 DM 1
European Union Aviation Safety Agency (n.d) Safety culture, EU-South East Asia Aviation Partnership Project (EU-SEA APP), EASA.
Federal Aviation Administration (2014). Advisory Circular 27-1B, accessed 4 June 2023.
Federal Aviation Administration (2013). Emergency procedures training,www.FAAsafety.gov, accessed 21 December 2022.
Federal Aviation Administration (2019). Helicopter Flying Handbook. FAA-H-8083-21B
Icer, M., Guloglu, C., Orak, M., Ustundag, M. (2013). Factors affecting mortality caused by falls from height. Ulus Travma Acil Cerr Derg, November 2103, 19(6):529-535 doi:10.5505/tjtes.2013.77535
Isenschmid, D.S. (2002), Cocaine – Effects on human performance and behavior. Forensic Science Review, 14:61; 2002.
Liu, C.-C., Wang, C.-Y., Shih, H.-C., Wen, Y.-S., Wu, J.-K., Huang, C.-I., . . . Huang, M.-S. (2009). Prognostic factors for mortality following falls from height. Injury – International Journal of the Care of the Injured, 40, 595-597.
Nau, C., Leiblein, M., Verboket, R.D., Hörauf, J.A., Sturm, R., & Marzi, I. (2021). Falls from Great Heights: Risk to Sustain Severe Thoracic and Pelvic Injuries Increases with Height of the Fall. Journal of Clinical Medicine, 10(2307):1-9. doi:https://doi.org/10.3390/jcm10112307
Papdimitriou-Olivgeris, M., Panteli, E., Koutsileou, K., Boulovana, M., Zotou, A., Marangos, M., Fligou, F. (2021). Predictors of mortality of trauma patients admitted to the ICU: a retrospective observational study. Brazilian Journal of Anesthesiology. 71:23-30.
Reason, J., 1998. Achieving a safe culture: theory and practice. Work & Stress, 12(3), pp. 293-306.
Shehab, R.L., Schlegel, R.E., and Palmerton, D.A., (1998). A human factors perspective on human external loads, The university of Oklahoma and FAA Civil Aeromedical Institute. Federal Aviation Administration. DOT/FAA/AM-98/13
Snyder, R.G. (1963). Human survivability of extreme impacts in free-fall. Civil Aeromedical Research Institute, Aeromedical Research Division. Oklahoma City: Federal Aviation Administration.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
pilot of VH-IDW
helicopter operator
helicopter maintainer
helicopter manufacturer
helicopter engine manufacturer
Civil Aviation Safety Authority
United States National Transportation Safety Board
Wild Harvest Northern Territory
emergency responders
other people involved in the egg collection operation
various subject matter experts.
Submissions were received from:
pilot of VH-IDW
helicopter operator
helicopter maintainer
helicopter manufacturer
Civil Aviation Safety Authority
Wild Harvest Northern Territory
emergency responders
other people involved in the egg collection operation
various subject matter experts.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Appendices
Appendix A – Fuel analysis
Initial fuel analysis
The ATSB drained the remaining fuel from VH-IDW after it was relocated to a hangar in Darwin. The observed blue colour of the fuel was consistent with 100 low-lead (LL) fuel. The fuel was stored in an unsealed container overnight resulting in some evaporation. The remaining 235 mL of fuel was sent to Intertek for testing to determine the fuel type. The initial tests requested were for fuel density and aromatics as these are key distinguishing properties between fuel types.
The density of the VH-IDW sample was 729.1 kg/m3 and contained 11.8 % v/v aromatics, see column 4 in Table 5.
The ATSB then obtained the invoices, fuel release notes and certificates of quality for the 100/130 Avgas fuel drums delivered to Mount Borradaile and the 2 most recent (prior to the accident day) batches of 100 LL Avgas delivered to the storage tank at Helibrook’s Noonamah base. In a submission provided following review of the ATSB draft report, Helibrook advised that VH‑IDW had been filled the night before the accident from its base at Sweets Lagoon, which also had 100 LL fuel. Fuel receipts showed 100 LL Avgas with batch density 718.3 kg/m3.
The fuel batch delivered in the drums to Mount Borradaile was green, had a density of 693.7 kg/m3 and 0.7% v/v aromatics, see column 3 in Table 5. The 100 LL fuel delivered to the Noonamah tank was blue, had a density of 715.4 and aromatics of about 15%, based on certificates of quality of recent fuel batches delivered to Darwin Port, see column 2 in Table 5.
The ATSB arranged for samples to be taken from 4 WHNT drums at Mount Borradaile, including the 2 identified as the drums used to refuel the R44 helicopters on the accident day. The first drum rolled out on the day was reportedly not full and its density was slightly higher than the batch testing as shown in column 5 of Table 5. The second drum closely matched the delivered batch results.
The initial comparison between the VH-IDW sample and 100 LL fuel indicated that the sample was consistent with partially evaporated 100 LL fuel. However, it was postulated that the reduction in aromatics could also result from a mixing of 100 LL and 100/130 fuel.
To determine whether the VH-IDW sample contained a proportion of 100/130 fuel, or any other fuel type, the ATSB liaised with 2 fuel experts – one from Viva energy, involved in the supply of the 100 LL Avgas, and the other in distribution of the 100/130 Avgas. The Viva expert suggested the ATSB request a distillation of the VH-IDW sample. The distillation process separates the sample into its component hydrocarbons. The sample would be heated then put into a distillation column where different products boil off at different temperatures. However, insufficient fuel remained from the VH-IDW sample to conduct that test. As an alternative, the Viva expert recommended conducting a simulated distillation, which only uses a very small quantity of fuel.
Intertek conducted the simulated distillation, which involved using a method for crude oil, with the results shown in column 4 of Table 5. The final boiling point obtained for the VH-IDW sample was significantly higher than the values stated in the certificates of quality for the batches of 100 LL and 100/130 fuels, and that obtained by using the normal fuel distillation method on the Mount Borradaile sample, all shown in row 9 of Table 5.
Table 5: Initial fuel test results
Tested property
100 LL delivered batch
100/130 delivered batch
VH-IDW sample
Mount Borradaile sample 4
Density @15 °C kg/m3
715.4
693.7
729.1
704.5
Aromatics %v/v
Est. 15%
0.7
11.8
N/A
Colour
blue
green
blue
green
Distillation Initial boiling point °C
38
36
58*
43
Distillation 10% °C
72
54
99*
85
Distillation 50% °C
102
102
112*
105
Distillation 90% °C
112
112
124*
113
Distillation final boiling point °C
139
131
188
130
Tetraethyl lead g-Pb/L
0.39
0.732
Inconsistent**
N/A
* Distillation for VH-IDW was done with incorrect method (used for crude oils not Avgas)
** Different TEL g-Pb/L values were obtained with 3 separate tests
The ATSB again consulted the Viva expert to understand the implications of the high final boiling point. They advised that, among other fuels, Jet A1 (kerosene) and unleaded car petrol have higher final boiling points than Avgas. This prompted further testing to determine whether the VH‑IDW sample was contaminated with another fuel type.
The Viva expert then liaised with Intertek on the ATSB’s behalf to conduct a gas chromatography test to analyse the hydrocarbons and compare the VH-IDW sample with Jet A1, unleaded petrol and 100 LL Avgas. They advised that the chromatogram of VH-IDW showed no traces of Jet A1, or unleaded petrol, but was consistent with partial evaporation of 100 LL Avgas. While this ruled out contamination with an unsuitable fuel type, it did not enable a determination of whether the VH‑IDW sample contained a significant proportion of 100/130 fuel.
As the lead content of 100/130 fuel is nearly twice that of the 100 LL, the Viva expert recommended that ATSB request Intertek conduct testing of the tetraethyl lead (TEL) content of the VH-IDW sample. The first test of the VH-IDW sample resulted in a value (1.370 g-Pb/L) which exceeded the test method upper limit of detection of > 1.3 g-Pb/L. Consequently, the ATSB requested Intertek retest the sample. Intertek conducted 2 subsequent tests of the VH-IDW sample and obtained values of 0.969 and 0.558 g-Pb/L.
Intertek was unsure why the results were inconsistent, and their final report stated they were unable to report a value due to the lack of a consistent result. Additionally, Intertek advised the ATSB that following the third TEL test, the colour of the VH-IDW fuel sample unexpectedly turned from blue to yellow-green. The ATSB then engaged the Defence Science and Technology Group (DSTG) for independent expert advice and provided all remaining fuel samples to DSTG.
The Viva expert’s assessment of the test results was that the VH-IDW sample was consistent with 100 LL Avgas that had undergone significant evaporation of the lighter boiling components. They assessed that there was no kerosene or road grade petrol in the sample. Based on the colour, prior to the sample turning yellow-green, they assessed that there was no more than 5% v/v of 100/130 fuel in the VH-IDW sample.
Defence Science and Technology Group analysis
Gas chromatography with mass spectrometry
DSTG conducted gas chromatography with mass spectrometry (GC-MS) analysis of the VH-IDW fuel and samples of blue 100 LL and green 100/130 Avgas fuel. The 3 resulting GC-MS traces were overlaid on each other for comparison. This showed that the VH‑IDW sample was missing, or had a very low concentration of, low boiling point compounds, consistent with evaporation. The DSTG report referenced a study performed by Canada’s Environmental agency, which found that a 33% evaporation of Avgas 100 LL resulted in a density change from 714.3 to 725.8 kg/m3 (CETC, 2022). Additionally, evaporation skews results such as distillation profile, TEL and total aromatics content. The evaporation skewed the trace for VH‑IDW towards the heavier side, exaggerating those peaks, including the peak for TEL. Tetraethyl lead was readily identified by DSTG using GC-MS, which showed a high concentration that could be attributed to evaporation and/or residual elements in the fuel tank.
The VH-IDW trace was more consistent with 100 LL than 100/130 fuel, although some extremely low concentrations overlapped with 100/130. This suggested that remnant fuel from previous days may have been detected in the GC-MS analysis. A comparison of the VH-IDW sample with the Mount Borradaile drum sample showed distinct differences in the GC-MC traces, and the VH-IDW sample had a significant number of peaks found only in 100 LL Avgas.
Ultraviolet-visible spectroscopy
The VH-IDW sample was blue when drained from the fuel bladder by the ATSB and when it arrived at Intertek. Following testing for TEL at Intertek, it turned a yellow-green colour. On arrival at DSTG, they described the VH-IDW sample as visually a deeper yellow-green than the 100/130 Avgas sample from Mount Borradaile and lacked the blue that was observed by ATSB investigators. DSTG therefore conducted ultraviolet-visible (UV-Vis) spectroscopy to compare VH‑IDW sample with 100 LL and 100/130 Avgas and, if possible, determine the source of the colour change.
Dyes were isolated using solid phase extraction and evaporated then dissolved in heptane prior to analysis. The UV-Vis spectra of the VH-IDW sample found blue dyes common to the Avgas 100 LL and 100/130 (batch and Mount Borradaile) samples. However, the VH-IDW sample did not contain a yellow dye found in the 100/130 samples. The absence of the yellow dye indicated 100/130 Avgas was not present in the VH-IDW sample at any significant concentration. DSTG subsequently assessed that there was likely less than 1% of 100/130 fuel in the VH-IDW sample.
The compounds contributing to the yellow-green colour were not in 100 LL or 100/130 Avgas and were not attributed to an approved yellow Avgas fuel dye. Further analysis to determine the likely source of the colour was ongoing at the time of the publication of this report.
Findings
The DSTG report found that the VH-IDW sample was consistent with Avgas 100 LL that had partially evaporated. The GC-MS trace of the VH-IDW sample significantly overlapped with the 100 LL sample. The UV-Vis spectra absorptions of the VH-IDW sample closely matched the dye for 100 LL Avgas. The 100/130 levels in the VH-IDW sample were assessed as trace volumes, subsequently approximated at less than 1% of otherwise 100 LL fuel. This was evidence that there was no refuelling of VH-IDW with 100/130 prior to the accident.
There was no evidence of Opal, premium 98 petrol, diesel or Jet A-1 fuel in the VH-IDW sample. The distillation method used by Intertek, although undertaken due to the small available volume of fuel, was for crude oil and not valid for other fuels. Consequently, the resultant high final boiling point was consistent with an incorrect test method rather than an accurate representation of the distillation profile.
At the time of writing, the nature of the colour contamination that occurred at Intertek was still under investigation.
Appendix B – CASA operational group risk matrix (2013)
Appendix C – HEC height, speed and distance/time conditions 2010–2021
Year
Height
Speed
Distance/time
2010-2013
The person is not lifted to a height of greater than 5 metres above the ground or obstacles
The aircraft is not flown at a ground speed greater than walking pace when the person is carried under the helicopter
The maximum distance the person is carried under the helicopter is 500 metres for each pick up
2014-2015
The person is not lifted to a height of greater than 5 metres above the ground or water. To remove doubt, this instrument does not permit lifting of a person to a height greater than 5 metres above an obstacle. The height restriction is in reference to the ground or water in all instances
The aircraft is to be flown at speed that is consider by the pilot in command to be a safe speed, taking into consideration the prevailing wind direction, wind speed, and aircraft performance when the person is carried under the helicopter. Minimisation of injury to the person in the event of hook release (whether planned or inadvertent release) must be considered in the context of the total forward speed of the person over the ground
The maximum distance the person is carried under the helicopter is 500 metres for each pick up
2016
The person is only to be lifted to a height above the ground or water that enables the person and aircraft to safely traverse over natural obstacles. In all other instances, the person is not to be lifted more than 5 metres above the ground or water. Minimisation of injury to the person in the event of hook release (whether planned or inadvertent release) must be considered in the context of the height the aircraft is operated above the ground or water at any particular time
The aircraft is to be flown at speed that is consider by the pilot in command to be a safe speed, taking into consideration the prevailing wind direction, wind speed, and aircraft performance when the person is carried under the helicopter. Minimisation of injury to the person in the event of hook release (whether planned or inadvertent release) must be considered in the context of the total forward speed of the person over the ground
The person is only to be carried for the minimum distance and time required in order to safely conduct the activity, taking the possible effects of suspension trauma on the person into consideration. To avoid any ambiguity, the intent of this condition is that the person is not to be carried for the purpose of positioning flights over landing sites where it would be possible to conduct the safe donning or removal of the person from the strop used to carry the person
2017-2021
N/A
The aircraft is to be flown at a speed that is considered by the pilot in command to be a safe speed, taking into consideration the prevailing wind direction, wind speed, and aircraft performance when the person is carried under the helicopter
The person is only to be carried for the minimum distance and time required in order to safely conduct the activity, taking the possible effects of suspension trauma on the person into consideration. To avoid any ambiguity, the intent of this condition is that the person is not to be carried for the purpose of positioning flights over landing sites where it would be possible to conduct the safe donning or removal of the person from the strop used to carry the person
This instrument is subject to the condition that the pilot in command and the operator must each ensure that:
1. The flying operations for the purpose of the activity are only done so utilising the Robinson Helicopter Company R44 helicopter type and only where the person and pilot in command both determine there is an overall safety advantage to the operation by reducing the risk of crocodile attack and heat exhaustion to the person; and
2. Persons other than crew members essential to the activity are not carried; and
3. Life jackets are worn by all crew members for all flights where the takeoff, positioning flights or approach path is so disposed that, in the event of a mishap occurring during operations, it is reasonably possible that the aircraft would be forced to land onto water; and
4. The pilot in command and the person have successfully completed a course of training for the activity promulgated in the operator’s operations manual which includes not less than 1 hour of actual flight time and 1 hour of ground instructional time; and
5. All crew, including the person being slung, have been inducted into the operator’s organisation, and have been included in the operator’s Drug and Alcohol Management Plan requirements; and
6. No pilot shall undertake the activity unless he or she has a minimum of 100 hours experience in helicopter external sling load operations; and
7. Only one person is carried below the aircraft at any one time; and
8. The chief pilot has personally authorised the flight program for the day associated with operations under this instrument; and
9. A thorough preflight briefing specifically related to each flight is conducted by the pilot in command to all personnel associated with the particular flight and is to include actions to be taken by crew members during possible emergencies encountered during the activity. The briefing is to be in accordance with, but not limited to, the activity briefing procedures promulgated in the operator’s operations manual; and
10. The pilot in command has continuous and clear radio communications with the person throughout the activity; and
11. The aircraft is to be flown at a speed that is considered by the pilot in command to be a safe speed, taking into consideration the prevailing wind direction, wind speed, and aircraft performance when the person is carried under the helicopter; and
12. Wind conditions, including wind gusts, for the area of proposed operation, must not exceed 15 knots; and
13. Operations not to be conducted within 5 kilometres of thunderstorm activity or observed lightning strikes. Should thunderstorm activity or lightning strikes be observed, activities under this instrument are to be terminated as soon as safely possible; and
14. The person is only to be carried for the minimum distance and time required in order to safely conduct the activity, taking the possible effects of suspension trauma on the person into consideration. To avoid any ambiguity, the intent of this condition is that the person is not to be carried for the purpose of positioning flights over landing sites where it would be possible to conduct the safe donning or removal of the person from the strop used to carry the person; and
15. The person wears a helmet that meets the Australian standard appropriate to the risks encountered during the activity; and
16. The person must wear an Australian Standard harness (designed for lifting a person) connecting them to the strop at all times during flight to and from the crocodile egg collection site. The person may be released from the strop during the actual process of crocodile egg collection; and
17. The person carries a readily accessible harness knife capable of cutting the lifting strop or harness in an emergency; and
18. All legislative requirements pertaining to the conduct of sling load operations are complied with; and
19. All normal and emergency equipment utilised for the conduct of the activity are serviceable; and
20. The helicopter carries a portable satellite phone with all crew members trained in its use; and
21. The person carries, and is trained to activate, a portable emergency location transmitter; and
22. Prior to the approval of CASA STC SVR 541, the aircraft must have been modified in accordance with, and remain compliant with, Engineering Order (EO) TDE5106-04-R2, dated 12/12/17 or later approved revision.
23. When CASA STC SVR 541 is approved, all aircraft previously certified to the EO will be shown to be compliant with and certified to the STC within fourteen (14) days of the STC being approved, after which time aircraft certified only to the EO may no longer undertake this work. Further aircraft to be used after the STC approval date will only be certified in accordance with the STC; and
24. Aircraft approved under EO TDE5106-04-R2 or later approved revision are to have the HEC Lines and harnesses installed and maintained in accordance with the EO approved data; and
25. Aircraft approved under STC SVR 541 are to have the HEC Lines and harnesses installed and maintained in accordance with the STC approved data; and
26. Other hook down equipment, such as collection basket/cages, helmets and other things will be determined by the Operator as being fit for purpose and meeting any required workplace or industrial standard; and
27. Aircraft operated under the EO TDE5106-04-R2 or later approved revision, are to be operated in accordance with an approved aircraft flight manual supplement R5106-101-R2 or later approved revision which details normal and emergency procedures associated with the activity; and
28. Aircraft operated under STC SVR 541 are to be operated in accordance with an approved aircraft flight manual supplement R5106-25-R9 or later approved revision which details normal and emergency procedures associated with the activity; and
29. The daily inspection schedule for each aircraft utilised for the activity incorporates detailed requirements for the inspection of any component, part or system utilised as part of human sling load operations; and
30. Prior to the commencement of the activity each day, the pilot in command has verified the aircraft engine is producing normal rated power output, and that no defects are evident which could lead to power reduction during those operations; and
31. Only persons employed or contracted for the purposes of the activity are carried. To avoid any ambiguity, this instrument does not permit persons who have provided consideration of any nature to any party to conduct egg collection activities or to be slung from the aircraft involved in such activities; and
32. The person must be provided with a copy of this instrument and must be made aware, in writing, that the hook system is not certified for human use; and
33. The operator and the pilot in command must comply with all applicable instructions relating to the activity contained within the operator’s operations manual. The operator must not, without the prior written consent of CASA, revise any part of its operations manual relating to the authorisation and permission given under this instrument.
Any breach of the conditions of this instrument will result in the instrument being immediately cancelled by CASA.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Long lines are lightweight, high‑strength, low‑stretch ropes used for carrying loads underneath a helicopter.
[2] Refuelling conducted while the engine(s) are operating and the rotors are turning.
[3] OzRunways is an electronic flight bag application that provides navigation, weather, area briefings and other flight information. It provides the option for live flight tracking by transmitting the device’s position and altitude.
[4] Loss of coordination of the muscles, especially of the extremities (Macquarie Dictionary).
[5] Safe work method statement (SWMS): a document that sets out high risk activities, the hazards associated with the activities and measures required to be in place to control the risks to an acceptable level.
[6] Normal category rotorcraft have a maximum take-off weight (MTOW) up to 3,175 kg and up to 9 passenger seats.
[7] Collective: a primary helicopter flight control that simultaneously affects the pitch of all blades of a lifting rotor. Collective input is the main control for vertical velocity.
[8] Manoeuvring with low fuel levels can result in fuel flowing away from the fuel tank outlet, or port, to the engine. This disrupts the engine fuel supply, resulting in power fluctuations and/or engine stoppage.
[9] Cyclic: a primary helicopter flight control that is similar to an aircraft control column. Cyclic input tilts the main rotor disc, varying the attitude of the helicopter and hence the lateral direction.
[10] A supplemental type certificate (STC) is a type certificate (TC) issued when an applicant has received regulatory approval to modify an aeronautical product from its original design. The STC, which incorporates by reference the related TC, approves not only the modification but also how that modification affects the original design.
[11] The primary hook could be used for non-human cargo lifting operations and, as such, could accrue more operational hours than the secondary hook (required for HEC operations).
[12] QNH: the altimeter barometric pressure subscale setting used to indicate the height above mean sea level.
[13] The altitude in the International Standard Atmosphere at which a given air density is found.
[14] B nut - threaded sleeve nut that provides clamping force to ensure an effective/good seal to fuel, air and oil lines.
[15] Due to engine installation orientation, the engine right magneto is located on the left side of the helicopter. Further, the engine right magneto contains a second set of points that provided a signal to the governor and engine tachometer.
[16] The lead content of 100/130 is about 0.732 g Pb/L and the lead content of 100 LL fuel is approximately 0.38 g Pb/L.
[17] Out of ground effect: helicopters require less power to hover when in ‘ground effect’ than when out of ‘ground effect’ due to the cushioning effect created by the main rotor downwash striking the ground. The height of ‘ground effect’ is usually defined as more than one main rotor diameter above the surface.
[18] The Pilot’s Operating Handbook (POH) incorporates the US Federal Aviation Administration-approved Rotorcraft Flight Manual.
[19] Autorotation is a condition of descending flight where, following engine failure or deliberate disengagement, the rotor blades are driven solely by aerodynamic forces resulting from rate of descent airflow through the rotor. The rate of descent is determined mainly by airspeed.
[20] This was CASR 11.055 (1)(d) in 2010 and CASR 11.055 (1A)(e) in 2013, but the wording is the same in both.
[21] Equivalent level of safety means an alternative action taken provides a level of safety equal to that provided by the requirements for which equivalency is being sought.
[22] The parachute landing fall is used to spread the forces of impact across various parts of the body to reduce the risk of injury. The landing position is with the knees slightly bent and feet together. The feet and toes contact the ground first, followed by a sideways roll onto the legs and torso then the back.
[23] A Failure Modes and Effects Analysis is a systematic method of identifying the failure modes and the failure outcome. The assessment may be quantitative or qualitative.
[24] Part 138 MOS definition: Class D external load means a load that is a person, carried external to the rotorcraft, by a rotorcraft in an external load operation.
[26] Transport Safety Investigation Regulation 2.4 (2)(e) and (2)(f)(i) specified that these occurrences were required to be reported if they occurred when the aircraft was boarded for flight and it involved the use of any procedure for overcoming an emergency or resulted in difficulty controlling the aircraft.
[27] Haemopneumothorax is the condition of having air and blood in the chest cavity.
[28] Subarachnoid haemorrhage is bleeding in the space that surrounds the brain.
Updates
Updated 31/10/2023: The ATSB is in receipt of directly involved parties’ submissions with their comments on the draft report, including information on any safety actions they have taken. As such the investigation is now in the ‘final report: approval’ phase, where the submissions are being assessed and the report is being prepared for final review and approval for public release by the ATSB Commission. Once approved by the Commission, the final report will be prepared for publication and dissemination. Public release is currently anticipated by the end of November.
Updated 04/10/2023:The ATSB has agreed to a brief further extension of the period afforded to directly involved parties to review and provide comment on the ATSB’s draft final report.
The ATSB will provide an update on timing for the public release of the report by the middle of October once all submissions from directly involved parties have been reviewed. The ATSB does not anticipate providing any further extensions to the involved parties review process.
The ATSB provides draft reports to directly involved parties to allow them to check the report’s factual accuracy and to ensure natural justice.
Updated 05/09/2023:Following receipt of the draft report as part of the ‘final report: external review’ phase, some extensions to the 14 day review period have been provided.
Given the complexity of this systemic-level investigation, the ATSB has agreed to extension requests commensurate with the interests of the involved parties.
An update on timing for the publication of the report will be provided at the end of September when the ATSB will have had an opportunity to review submissions.
Updated 28/08/2023: The ATSB’s investigation into the collision with terrain involving Robinson R44, VH-IDW, King River, Northern Territory, on 28 February 2022, is now in the ‘final report: external review’ phase.
After the draft final report was reviewed by ATSB management, the ATSB Commission approved providing the draft report to directly involved parties (DIPs) to allow them to check the report’s factual accuracy and to ensure natural justice.
DIPs are individuals or organisations who possess direct knowledge of the circumstances surrounding the accident.
The draft report was provided to DIPs under Section 26(1)(a) of the Transport Safety Investigation Act 2003. Under Section 26, the report may only be copied and disclosed for the purpose of taking safety action or providing comment to the ATSB. Anyone who receives a copy for these purposes is also bound by the confidentiality requirements.
Disclosure of the draft report in any other circumstance may constitute a criminal offence.
ATSB draft reports may contain information that is subject to change as a result of internal and external review and consideration of further evidence. In its draft form, copying or disclosing the report may unjustly affect reputations. This in turn could potentially impede and discourage the crucial, future free flow of safety information to the ATSB.
Directly involved parties have been provided 14 days to provide any comments on the draft report and to present evidence in support of their comments.
Any submissions from directly involved parties will then be reviewed and, where considered appropriate, the text of the report will be amended accordingly.
The report will then be reviewed by ATSB management before approval by the ATSB Commission for public release.
Once approved, the final report will be prepared for publication and dissemination and released to DIPs prior to its public release.
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On 28 February 2022, the crew of three Robinson R44 helicopters were preparing to conduct crocodile egg collection in Arnhem Land, Northern Territory. The egg collection was conducted under contract to Wildlife Harvesting (Northern Territory).
Each helicopter had two crewmembers – one nominated pilot in command and one egg collector. Two of the helicopters were operating under a Civil Aviation Safety Authority Instrument. The instrument authorised the pilot in command to operate with a person outside the aircraft in a harness system attached to the helicopter for the purpose of collecting crocodile eggs. The authorisation was subject to a number of conditions, which included fitment of equipment under an Engineering Order or a Supplemental Type Certificate and an associated flight manual supplement.
The two helicopters used for sling operations were fitted with dual external cargo hooks, which attached to rings on a 100 ft long line. This enabled the egg collector (‘sling person’) to be slung 100 ft below the helicopter to access the nests. The line could be released by the pilot via a quick release system for the cargo hooks. The cargo hooks were fitted with primary and back-up dual quick release systems, to reduce the likelihood of inadvertent pilot activation and provide redundancy in case of failure. One of those two helicopters was an R44 Raven II, registered VH-IDW, operated by Helibrook Pty Ltd. The third helicopter was primarily to be used for transporting eggs, although both its pilot and collector also collected eggs on foot and wore a harness so they could be slung under either of the other two helicopters as needed.
At about 0703 Central Standard Time,[1] the three helicopters departed from Noonamah, for a 90-minute flight to a site where fuel drums had been pre-positioned en route to the collect sites. Fuel was available at Noonamah and the drum site, however, there were no accurate records of fuel uplift for VH-IDW.
The helicopters departed from the drum site at about 0830 and tracked to the King River staging area, where the crews prepared to commence egg collection operations (Figure 1). Recorded OzRunways[2] data for two of the helicopters recorded their arrival at the staging area at 0850. The pilot and sling person of VH‑IDW planned to start the egg collection from a nest located close to the staging area. At about 0900, the other two helicopters departed the staging area for their crew to commence collecting eggs about 12 km to the north-east. Data recorded for the egg collection showed that the crew of those two helicopters collected eggs from nine nests between 0911 and 1014.
By 1014, the four crewmembers operating to the north-east became concerned that they had not heard any radio communications from the crew of VH-IDW since departing the staging area. As a result, one of the pilots elected to return to the area they expected VH-IDW to be operating in. At 1036, the pilot located the wreckage of VH-IDW and landed near the accident site (Figure 1). They found the helicopter substantially damaged having collided with trees and terrain. The sling person was deceased, and the pilot had sustained serious injuries. After providing reassurance to the pilot of VH-IDW, the other pilot returned to their helicopter and took off briefly to get mobile reception and call for assistance. A Careflight helicopter arrived on site at about 1230 and airlifted the pilot to Maningrida, where they were transferred to an aeroplane and flown to Darwin.
The location of the accident was in the vicinity of the first target nest for egg collection by the crew of VH-IDW. No eggs had been collected, indicating that the accident probably occurred about 90 minutes before it was found. A handheld emergency position indicating radio beacon and the helicopter’s emergency locator transmitter, which was not mounted in the installed airframe rack or armed in case of emergency, were subsequently found in helicopter. Neither was activated to alert rescue personnel at the time of the accident.
Figure 1: Accident area including King River, staging area, accident site and the approximate tracks of the other two helicopters
Source: Google earth overlaid with positions obtained from OzRunways and collection data
Context
Site and wreckage
The accident site was located in a paperbark swamp approximately 300 m from the staging area. Preliminary analysis of the site indicated that the accident sequence had occurred in a north‑westerly direction. The sling person was found approximately 40 m prior to the main wreckage. The long line attachment rings were not connected to the helicopter cargo hooks. Although the pilot reported that they had been wearing the 4‑point seat restraint, the pilot had egressed the helicopter and lay beside it.
The helicopter’s main rotor blade had struck and cut through the trunk of at least one tree at multiple points before the helicopter collided with terrain upright, facing north-east (Figure 2). The helicopter’s skids had splayed and fractured, and the base of the pilot’s seat had crushed as designed to absorb impact forces.
Figure 2: VH-IDW accident site
Source: Careflight
Initial assessment indicated that the engine was stopped when the helicopter collided with the ground. There was no visible damage to the tail rotor blades and continuity of the drive system and flight controls was established.
The two fuel bladder tanks were intact despite breaches of the surrounding metal tanks and there was no fire. However, the fuel system was compromised in the accident, and it was possible fuel escaped into the creek that flowed beneath the wreckage. After initial assessment, the helicopter wreckage was retrieved from the site. ATSB investigators subsequently drained about 250 ml of blue fuel from the main tank’s bladder.
Engine examination
The engine and associated components were taken to CASA-authorised maintenance facilities for examination under supervision of the ATSB. The examinations did not identify defects of the engine likely to result in engine stoppage.
Pilot qualifications and experience
The pilot held a Class 1 Medical Certificate, a Commercial Pilot Licence (helicopter) and a low-level helicopter rating. At the time of the accident, the pilot had a total aeronautical experience of about 2,500 hours.
Weather
The weather recorded at 0900 at the two nearest Bureau of Meteorology weather stations was:
Warruwi (Goulburn Island) 30 km north of the accident site: west-north-westerly wind at 13 km/hr, QNH 1009.6 hPa, temperature 28.8 °C.
Maningrida 90 km east of the accident site: westerly wind at 6 km/hr, QNH 1009.1, temperature 27.5 °C.
At sea level QNH 1009 hPa and 28 °C, the density altitude is 1,680 ft.
Further investigation
The investigation is continuing and will include review and examination of:
electronic components retrieved from the accident site
fuel system components
refuelling practices
fuel quality
maintenance records
operational documentation
regulations
survivability aspects.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Acknowledgements
The ATSB would like to acknowledge the assistance of Careflight, the Northern Territory Police and Nautilus Aviation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 23 February 2022, a Piper Aircraft Corporation PA-25-235/A9, registered VH‑SEH, was conducting agricultural spreading operations from a private landing area located near Seaview, Victoria. At 0711, the pilot commenced take-off for the first load of the day. The aircraft accelerated along the prepared strip and briefly became airborne. The outboard section of the aircraft’s left wing impacted trees and detached from the aircraft. The aircraft rolled to the left, pitched down, and collided with terrain. The pilot, who was the sole occupant, was fatally injured and the aircraft was destroyed.
What the ATSB found
The ATSB found that the take-off was attempted at an aircraft weight that likely did not permit sufficient performance to clear the trees at the end of the strip. Although the pilot had conducted take-offs using the Seaview runway strip in previous years, the increased height of trees at the northern end of the strip were found to have reduced safety margins to some extent.
It was also identified that engine power during take-off may have been slightly lower than normal. This may have been due to the water content of the air, carburettor ice, or the carburettor heat selector may have been inadvertently left on during the take-off. However, a conclusion regarding the existence of these scenarios could not be drawn with any certainty.
The ATSB also found that the pilot likely initiated a jettison of the hopper contents shortly after becoming airborne, but any effect this had on the aircraft’s performance was probably negligible.
Safety message
Aircraft operators and pilots are reminded of the hazards associated with operations from small landing areas that are not prepared as permanent runways. In any case, pilots should ensure aircraft loads are within specified limits, appropriate for the environmental conditions, and will result in the required performance to maintain safety margins.
The investigation
Decisions regarding the scope of an investigation are based on many factors, including the level of safety benefit likely to be obtained from an investigation and the associated resources required. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On 23 February 2022 at about 0650 local time, the pilot of a Piper Aircraft Corporation PA-25-235/A9, registered VH-SEH, departed Leongatha Aerodrome, Victoria, for a positioning flight to a private landing area[1] situated 25 km to the north in the locality of Seaview. The aircraft was reportedly carrying full fuel (170 L) prior to take-off.
The aircraft landed at about 0700 in preparation for the aerial spreading of superphosphate pellets. The pilot had been tasked to spread 41,000 kg of superphosphate fertiliser at 6 nearby properties. It was anticipated this would take about 80 loads and 8 hours to complete.
The loader driver[2] for the day’s activities arrived at the Seaview landing area at about 0705. On arrival, the loader driver found VH‑SEH parked with the engine stopped and the pilot out of the aircraft. The pilot had filled the loader’s bucket with superphosphate prior to the arrival of the loader driver.
The loader driver and the pilot had a short conversation and the pilot returned to the aircraft. The loader driver transferred the superphosphate to the aircraft’s hopper with the pilot on board the aircraft. The loader driver could not see how much superphosphate had been loaded into the bucket, and the weighing system in the loader only indicated weight at the time of filling the bucket.
The loader driver then parked the loader at the southern end of the landing area and prepared for the next load. A short time later, the pilot started the aircraft’s engine and remained at the southernmost point of the landing area for about 5 minutes.
Based on local weather observations and a witness’s video recording of the take-off, the weather at the time of the accident was fine with the wind likely calm. The loader driver described the weather conditions at the time as good.
According to witness reports, the pilot was wearing a 4-point harness and a helmet. Data from an onboard GPS device showed that the pilot commenced the take-off on the prepared runway strip at about 0711 (Figure 1).
The runway strip went downhill, and then uphill, where it branched into 2 sections. According to the 2 witnesses and the recorded video, the aircraft accelerated along the strip and traversed the right section where the strip divided.
The aircraft briefly became airborne at a point at the end of the strip where the terrain dropped away. The outboard section of the aircraft’s left wing then impacted trees and separated the left outboard section of wing. The aircraft rolled to the left, pitched down, and collided with terrain about 30 m beyond the trees (Figure 2). The pilot was fatally injured and the aircraft was destroyed.
Figure 1: Runway strip overview
Source: ATSB
Figure 2: End of runway strip and impact points
Source: ATSB
Context
Pilot information
The pilot held a valid class 1 aviation medical certificate and a commercial pilot licence (aeroplane), having completed a flight review and an aerial application proficiency check on 11 November 2021. At the time of the accident, the pilot had about 12,350 hours total aeronautical experience. The pilot was the owner and chief pilot of the aerial work operator, which conducted mostly aerial application activities.
The pilot was reported to be fit and healthy and there was no indication they were experiencing a level of fatigue known to affect performance. The post-mortem and toxicology examinations did not identify any indicators of incapacitation or substances that could have affected the pilot’s capacity to perform the flight.
Aircraft information
General information
The aircraft was a 2-seat Piper Pawnee PA-25-235/A9 with a 6-cylinder, normally aspirated Textron Lycoming O-540-H2A5 engine driving a 2-blade McCauley Propellers 1A200/FA8452 fixed-pitch propeller (Figure 3). This propeller was designed for increased efficiency during cruise compared with other propeller options, but also resulted in decreased climb performance and increased the take-off distance required. The propeller was first installed on the aircraft in March 2019.
Figure 3: A similar Piper PA-25-235/A9 configured for agricultural spreading
Source: ATSB
The aircraft was originally manufactured as a single-seat PA-25-235 in 1974. In 1988, the aircraft was involved in an accident while conducting herbicide spraying near Deddick Park, Victoria. The outboard section of the right wing collided with a tree. The aircraft climbed steeply then descended in a nose-down attitude and impacted terrain.[3]
In 1989, the aircraft was rebuilt and converted to an ‘A9’ variant. This conversion included the installation of a second seat (in a side-by-side configuration), replacement of the fabric-covered wings with metal wings, the installation of a larger chemical hopper, and the fitment of a larger Lycoming O-540-H2A5 engine. Flying controls were on the left side.
The engine was last overhauled in March 2021, and the last periodic inspection was carried out in July 2021 with no defects recorded. At the time of the accident, the aircraft had accumulated 9,543.5 hours total time in service, and the engine had accumulated 159 hours since overhaul.
Aircraft hopper
The hopper was located between the instrument panel and the engine firewall. It was constructed from fiberglass and had a 544 kg maximum permissible load. Its volume (200 gallons, or 757 L) was sufficient to hold up to about 800 kg of superphosphate pellets. There was a clear section in the cockpit, with graduations in gallons, to enable the pilot to see how much volume of product was in the hopper.
The quantity of superphosphate on board the aircraft during the take-off could not be determined. Those familiar with the recent operating practices of the pilot of the accident flight reported that, if weather and strip surface conditions were favourable, it was normal for the pilot to take a full load of superphosphate on the first flight from a landing area. Otherwise, the pilot would normally opt to take a reduced load on a first flight. A typical reduced load for this pilot was reported as being about 400 kg.
The aircraft was fitted with an emergency hopper dump mechanism. The mechanism allowed a pilot to dump all or part of the hopper contents if the aircraft did not achieve the required performance. To do so, the pilot would push a button on the spread/dump lever (to enable the lever to move past a gate) and move the lever past the spread selection to the full forward position. This would fully open the hopper door located on the underside of the aircraft fuselage. A full load of superphosphate was expected to completely jettison in about 4 seconds. Dumping the hopper load would significantly, and almost immediately, reduce the aircraft’s weight and increase performance.
The total elapsed time from the aircraft becoming airborne to impacting the trees was 2 seconds.
Performance
The approved flight manual for VH‑SEH contained take-off performance charts that could be applied to calculate a performance-limited maximum take-off weight using aircraft and environmental parameters for a given flight. These charts included a wet or dry surface and long or short grass. Such charts had reduced applicability for landing areas with significant changes in slope, and rough surface conditions were not captured by the charts. The aircraft operator’s operations manual (OM) contained the responsibilities for company pilots. The OM stated:
In determining that an operation can be conducted safely, the pilot will consider:
a) carriage of heavier than manufacturers’ recommended weights
b) strip length and conditions, particularly in relationship to the performance parameters of the particular aircraft used by the Company
c) strip altitude and density altitude
d) wind speed and direction, especially any downwind component
e) obstacles
The OM also stated:
Pilots are responsible for the safety of the aircraft. Many accidents have loading as a causal factor. That is, the aircraft may have flown off the same landing area with the same load but slightly different environmental conditions. The decision to dump a load may be relatively cheap when compared to repairing an aircraft. The ability to dump the load is the last line of defence in the accident chain but it remains a very good defence and should be used as required. Pilots should make a conscious decision on each take off about how much load they will take and at what stage they will either abort take-off or dump the load in the event that the aircraft fails to become airborne at the expected time. To make this decision, pilots should have firmly in their mind where the aircraft should get airborne.
The ATSB undertook performance calculations using known and estimated aircraft and environmental information, including fuel and hopper loads. It was estimated that the aircraft was probably near the performance-limited maximum take-off weight for a level (no slope) strip the same length as the actual strip, without any load in the hopper. Using an estimated weight range for the hopper load of 400–544 kg, the aircraft would have been over the performance-limited maximum take-off weight for an equivalent-length level strip. This range of hopper loads would have resulted in a take-off weight of about 1,400–1,544 kg. The aircraft’s maximum take-off weight was 1,315 kg.
Carburettor heat
Carburettor icing occurs when water vapour freezes within an engine’s carburettor due to a decrease in temperature and pressure within the carburettor. The likelihood of carburettor icing increases with humidity and at partial power settings (for example, when idling). If ice accumulates within a carburettor, the flow of air to the engine (and, ultimately, available power) reduces.
A carburettor heat control was available in VH‑SEH. When selected, warm air was directed from a heat exchanger on the exhaust system to the carburettor inlet, melting any ice in the carburettor. The operator’s other pilots reported that it was standard practice to apply carburettor heat during ground operations, selecting it off just prior to commencing the take-off. The purpose of this practice was to prevent carburettor ice build-up during engine idling.
It was reported that the application of carburettor heat in VH‑SEH would result in a propeller speed reduction of about 100 RPM and, if inadvertently left on during take-off, would significantly increase the take-off distance required. Due to the level of damage, the ATSB could not determine the position of the carburettor heat control at the time of the accident or whether carburettor icing occurred during the take-off.
Water vapour and engine performance
High concentrations of water vapour within the air (a high relative humidity) can impact engine performance. The water vapour alters the fuel to air ratio, causing enrichment, as well as reducing the burning and cooling efficacy of the engine. This reduces the power output of engine and may increase the take-off distance required. The ATSB could not determine the relative humidity at the landing area at the time of the accident (see also Weather information).
Runway strip
The runway strip at Seaview was prepared annually for aerial agricultural operations by the operator of VH‑SEH. The prepared strip had been mowed into a ‘Y’ configuration by the pilot of the accident flight in the days before the accident. It consisted of mowed grass and the surface was hard and rough from previous cattle movements. The strip was at an elevation of about 1,100 ft above mean sea level (AMSL) and each branch provided about 360 m take-off and landing distance on the ground.
Take-offs were always conducted in the same direction due to the more downwards slope. In this direction, the strip followed the natural terrain, with a downwards then upwards slope before dropping steeply towards the stand of trees. The left branch was oriented to the left of the trees and the right branch was oriented directly towards the trees (Figure 4).
Figure 4: Runway strip ‘Y’ intersection showing the left and right branches with the trees at the runway’s end
Source: ATSB
The pilot had not operated from this strip for at least 2 years prior to the accident. It was reported that the trees at the end of the strip had grown about 3–10 ft during that time. The pilot was reportedly aware of the hazard presented by the trees, having commented on their growth over the years. In the days prior to the accident, the pilot had communicated their intent to use the right side of the prepared strip for the day’s operations. Another of the operator’s pilots reported preferring the left branch of the strip in order to avoid the trees. The reasons for the accident pilot’s preferred use of the right branch could not be determined.
Site and wreckage
The wreckage was located about 30 m north of the stand of trees at the northernmost end of the strip. The trees were about 90 ft in height above ground level (AGL). Damage to the trees indicated the left wing impacted the trees at a height of about 74 ft AGL. Examination of the accident site indicated the aircraft impacted the ground inverted with an angle of entry of about 50° with the left wing low, and came to rest about 8 m from the initial impact point. The cabin sustained significant damage (Figure 5). Significant curved compression damage was evident on the leading edge of the left wing consistent with tree impact damage (Figure 6).
Figure 5: Aircraft wreckage
Source: ATSB
Figure 6: Outboard section of left wing with tree impact damage
Source: ATSB
The hopper door was open, and superphosphate had spilled from the hopper with most in the vicinity of the fuselage. Superphosphate was also found in smaller quantities near the initial impact point with the trees and scattered from halfway between the aircraft’s point of take-off to the wreckage site. The scattered pellets were consistent with a pilot-initiated release (and not post-impact scatter); however, it could not be determined if the mechanism had been activated in the spread or emergency dump position. The position of the spread/dump lever at the time of impact could not be determined.
Examination of the propeller, along with ground marks, indicated the propeller was rotating under power at the time of impact.
External examination of the engine did not identify any obvious defects. The engine tachometer displayed a needle ‘slap mark’[4] indicating about 2,240 RPM.[5] The throttle position at the time of impact could not be determined due to disruption of the controls.
There were no evident pre-impact defects with the aircraft structure and flight control continuity was confirmed as far as possible. The flap handle was in the top notch, indicating full flap. The operator’s other pilots reported that it was normal practice to apply full flap at the lift-off point, followed by a gradual reduction of flap setting as the aircraft climbed away.
ATSB analysis (based on estimates of the aircraft’s speed, impact angle and damage to the aircraft) indicated the impact forces for this type of accident would normally be expected to result in fatal injuries irrespective of any safety equipment worn.
Weather information
Recorded meteorological data for the landing area was not available. The weather conditions captured on the video recording made by a nearby witness included no cloud, visibility greater than 10 km and wind calm.
At the time of take-off, there was no fog at the landing area, there was a layer of fog in a nearby valley below the landing area. Given the proximity of the fog (saturated airmass), it indicates that conditions conducive with reduced engine performance and/or carburettor icing may have been present at the landing area. Recorded information
Accident video
The video recording captured by the witness was 30 seconds in length and commenced 6 seconds prior to the initiation of the take-off roll, ceasing 1 second after the aircraft impacted trees. No anomalies were evident in engine sound recorded on the video, such as rough running or power reduction during the take-off roll.
Audio spectrogram analysis of the video recording indicated that the aircraft’s propeller speed was likely about 2,357–2,587 RPM during the take-off roll, and this was maintained until the collision with the trees. The operator’s other pilots indicated that a typical propeller speed for VH‑SEH during take-off was about 2,500 RPM.
Global positioning system
A Tracmap Aviation TMA384 GPS device was recovered from the accident site and the stored data was downloaded. The data captured the aircraft’s arrival at the Seaview landing area, and the moments prior to take-off, but the device did not capture the subsequent take-off or the accident sequence. This was probably due to power supply disconnection during impact, preventing data being written to the memory card.
Safety analysis
The accident flight was the first load of the day and the aircraft had almost full fuel on board. Although the amount of superphosphate loaded onto the aircraft could not be determined, it was likely that the aircraft’s weight exceeded the performance-limited maximum take-off weight for the strip as well as the aircraft’s documented maximum take-off weight. This likely degraded the aircraft’s take-off performance significantly and contributed to the aircraft being unable to clear the stand of trees downslope of the lift-off point.
Additionally, the tachometer slap mark and the audio spectrogram analysis of the video recording indicated the power generated by the engine during the take-off may have been slightly lower than normal. No obvious defects were identified with the engine and the propeller was rotating under power at the time of impact. The relative humidity at the time of take-off could not be established. However, it is possible the aircraft’s engine performance was negatively impacted by the volume of water present within the air, affected by carburettor ice, or the carburettor heat selector may have been inadvertently left on during the take-off. Although these scenarios could explain a reduced propeller speed, there was insufficient evidence available to determine whether these events took place.
Although the pilot had conducted take-offs using the Seaview runway strip in previous years, the increased height of trees at the northern end of the strip had reduced safety margins to some extent. The aircraft struck the trees about 16 ft from the top, which meant that even without their estimated 3–10 ft extra height, there would not have been sufficient clearance for a safe take-off.
The investigation was unable to determine why the pilot elected to prepare, and use, a strip orientated directly towards the trees when an alternate take-off option was available.
A limited number of superphosphate pellets were found scattered between the aircraft’s point of take-off and the location where the aircraft impacted the ground. This indicated the pilot likely attempted to jettison the hopper contents around the time of becoming airborne. However, the effect this jettison would have had on the aircraft’s performance was probably insufficient for it to clear the trees, given that it would have had to gain about 16 ft in 2 seconds with some of the load still on board.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision with terrain involving Piper PA-25, VH-SEH, near Seaview, Victoria, on 23 February 2022.
Contributing factors
The take-off was attempted at an aircraft weight that did not permit sufficient performance to clear a stand of trees downslope of the lift-off point. As a result, the aircraft impacted the trees and collided with terrain.
Other factor that increased risk
Although successful take-offs had been made using the prepared strip in previous years, the increased height of trees at the end of the strip reduced the safety margins over time.
Other findings
The pilot likely attempted to jettison the hopper contents shortly after becoming airborne. However, the jettison would have only been partially completed by the time the aircraft collided with the trees, and there had probably been insufficient time for the aircraft to gain enough height to clear them in the intervening period.
Sources and submissions
Sources of information
The sources of information during the investigation included the:
Bureau of Meteorology
operator, 2 of the operator’s other pilots and loader driver
Civil Aviation Safety Authority
Victoria Police
maintenance organisation
witness and witness video.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the Civil Aviation Safety Authority
the operator.
A submission was received from a party familiar with the operator’s activities. The submission was reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Landing area: a place, whether or not an aerodrome, where an aeroplane is able to take off and land.
[2] Loader driver: an operator of loading equipment to support aerial application operations.
[3] ATSB investigation 198801404, Piper PA25-235 (Pawnee), VH-SEH, "Deddick River" (24 km NE of Gelantipy) Victoria, 9 November 1988.
[4] Needle slap mark: an imprint made on the gauge face by the instrument’s needle at time of impact.
[5] The propeller speed prior to the aircraft impacting the terrain would have been higher than indicated by the slap mark due to the slowing of the engine during the impact sequence, as well as the angle of impact tending to push the needle left just before making the mark.
Preliminary report
Report release date: 28/06/2022
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On 23 February 2022, at about 0650 Eastern Daylight-saving Time,[1] the pilot of a Piper Aircraft Corporation PA-25-235/A9, registered VH-SEH, departed Leongatha Aerodrome, Victoria, for a positioning flight about 25 km north to a private landing area[2] at Seaview.
The aircraft landed at about 0700 in preparation for aerial spreading of superphosphate pellets. The loader driver[3] arrived shortly after, finding that the loader’s bucket had been pre-filled by the pilot. The loader driver transferred the superphosphate to the aircraft’s hopper with the pilot on board. The loader driver could not later recall how much superphosphate had been loaded.
The loader driver then parked the loader at the southern end of the landing area and prepared for the next load. A short time later, the pilot started the aircraft’s engine and remained at the southernmost point of the landing area for about 5 minutes.
Based on local weather observations and a video recording made by a nearby witness, the weather at the time of the accident was fine with the wind likely calm.
Data from an onboard GPS showed that the pilot commenced the take-off on the prepared runway strip at about 0711 (Figure 1). According to witnesses and the recorded video, the aircraft accelerated along the prepared strip and traversed the right section where the strip split into 2 directions. The aircraft briefly became airborne at a point at the end of the strip, where the terrain dropped away, before the outboard section of the aircraft’s left wing impacted trees. The aircraft rolled to the left, pitched down, and collided with terrain about 30 m north of the trees (Figure 2). The pilot was fatally injured and the aircraft was destroyed.
Figure 1: Landing area overview
Source: ATSB
Figure 2: Landing area overview showing approximate lift-off point, impact with trees and ground impact point
Source: ATSB
Context
Pilot information
The pilot held a valid class 1 aviation medical certificate and a commercial pilot licence (aeroplane), having completed a flight review on 30 October 2020 and a proficiency check on 11 November 2021. At the time of the accident, the pilot had about 12,350 hours total aeronautical experience.
The pilot was the operator’s owner and chief pilot.
Aircraft information
The aircraft was a Piper Pawnee PA-25-235/A9 with a 6-cylinder, normally-aspirated Textron Lycoming O-540-H2A5 engine driving a 2-blade McCauley Propellers 1A200/FA8452 fixed-pitch propeller (Figure 3).
Figure 3: Another Piper PA-25-235/A9 configured for agricultural spreading
Source: ATSB
The aircraft’s hopper could hold up to about 700 kg of superphosphate pellets, but its maximum permissible hopper load was 544 kg (considered a full load by the operator’s other pilots). There was a clear section in the cockpit to enable the pilot to see how much volume of product was in the hopper.
The exact volume or weight of superphosphate loaded into the aircraft’s hopper could not be determined. The operator’s other pilots reported that it was normal to take a full load of superphosphate on the first flight from a landing area unless weather and strip surface conditions were unfavourable. In these scenarios, the pilot could opt to take a half load as a first flight.
Landing area
The landing area was normally used for cattle grazing and was prepared as a landing area for aerial application operations once a year. The pilot had not operated from the landing area since 2019.
The prepared strip had been mowed into a ‘Y’ configuration by the pilot in the days before the accident. It consisted of mowed grass and the surface was rough from previous cattle movement in wet soil. The strip was about 360 m in length and followed the natural terrain, with a downwards then upwards slope before the terrain dropped steeply towards a stand of trees about 60 m from the northernmost end of the strip. The left of the ‘Y’ was oriented to the left of the trees and the right of the ‘Y’ was oriented directly towards the trees (Figure 4).
Figure 4: Runway strip Y intersection showing the left and right take-off options with the trees at the runway’s end
Source: ATSB
Site and wreckage
The ATSB conducted an on-site examination of the aircraft wreckage (Figure 5). The aircraft impacted the ground inverted with an angle of entry of about 50°. There were no evident pre-impact defects with the flight controls or aircraft structure, and external examination of the engine did not identify any obvious defects. The propeller damage was indicative of the engine driving the propeller with significant power at impact. Preliminary audio analysis of the witness video indicated that the engine was at or close to its maximum rotational speed throughout the take-off.
Figure 5: Wreckage of VH-SEH
Source: ATSB
Further investigation
The investigation is continuing and will include:
pilot records
aircraft records
aircraft weight and balance
aircraft take-off performance
further analysis of the witness video recording and downloaded GPS data.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On 14 February 2022, the pilot of a Garlick UH-1H helicopter was supporting the Tasmania Fire Service (TFS) by providing aerial firebombing support to the Lebrina bushfire, in northern Tasmania. The pilot was requested by TFS to provide firebombing assistance to combat a spot fire that had flared up on the western flank of the fireground and at 1509 local time the pilot departed the TFS staging area. After transiting to a nearby dam and loading water into the underslung bucket, the pilot tracked toward the spot fire.
Witnesses observed the unexpected early release of water from the underslung bucket prior to reaching the target, before the helicopter tracked away from the location of the spot fire toward an open paddock. As the helicopter approached the paddock, the helicopter was observed to rotate rapidly before pitching steeply nose-down and descending. The helicopter collided heavily with terrain in a tail low, upright orientation before coming to rest on its left side. A post‑impact fire started in the engine bay, destroying the helicopter. The pilot received fatal injuries.
What the ATSB found
During the conduct of a firebombing operation, the helicopter’s engine-to-transmission main KAflex drive shaft partially failed and entered fail-safe mode. That resulted in the pilot jettisoning the water load from the underslung bucket and diverting toward clear ground. The failure was likely due to the fracture of a flex frame attaching bolt, or a flex frame element during the accident flight.
As the helicopter was slowing during a descent over clear ground, the KAflex subsequently completely failed, resulting in instantaneous loss of drive to the rotor system.
Following loss of drive to the main rotor system, the pilot was unable to complete a survivable autorotative descent and landing, probably due to a critical reduction in main rotor speed.
What has been done as a result
Following the accident, the Civil Aviation Safety Authority released 2 updates to a previously released Airworthiness Bulletin on the subject of pre-flight inspection requirements for the KAflex drive shaft. The Airworthiness Bulletin recommended that maintainers and operators check the condition of all drive shaft hardware in addition to the pre-existing inspection requirements listed in the flight manual. The bulletin also provided further advice to operators and maintainers on potential operational aspects once a KAflex has entered fail-safe mode.
The ATSB released a safety advisory notice (SAN) in June 2022 to all operators of UH-1H helicopters advising of the circumstances surrounding the accident and that it involved failure of the KAflex driveshaft. The SAN advised operators of UH-1H helicopters to note the details of this accident and to look for the presence of red metallic residue or debris at the bolted connections, frame cracking, missing or damaged attaching hardware during all inspections of the KAflex driveshaft. Any identified defects should be notified to the Civil Aviation Safety Authority.
Additionally, the SAN also advised that operators should be aware of the KAflex manufacturer’s (Kamatics) concern regarding shafts for the UH-1H helicopter that may be fitted with legacy attachment hardware. Kamatics should be contacted if a shaft, serial number 0635 and below, is identified.
Richmond Valley Aviation, the maintainer and operator of the accident helicopter, advised that following the accident they removed all KAflex main transmission drive shafts from the helicopters that they maintained and replaced them with an alternate type of shaft that can be greased.
Kamatics advised that for KAflex shafts returned to their factory a teardown inspection will be completed to identify any evidence of fretting, cracked washers or any other undesirable defect in hardware items normally replaced during overhaul.
The Tasmania Fire Service advised that, since the accident they have completed the following agency safety actions in relation to their aviation operations:
Transitioned to the Tasmanian Government Radio Network to enable direct communications with other emergency service organisations, fire land managers and aircraft operators working at multi-agency incidents.
Conducted an inter-agency exercise to test the response to a rescue incident in remote and isolated areas. The exercise tested the TFS timelines, incident management command and control, communication links, processes and roles of each agency. A key outcome was that the notification procedures have been improved between TFS, Tasmania Police and the Ambulance Tasmania Air Rescue Aviation Unit.
Safety message
Pilots of UH-1H helicopters should note that if vibrations or noise from the transmission area rapidly increases or becomes severe during flight, it may signify that the KAflex drive shaft has entered fail‑safe mode and could imminently fail.
Significantly, the commencement of a distinct ‘howling’ or ‘shrieking’ noise is a key indication of a developing KAflex failure.
The ATSB strongly recommends that pilots land as soon as possible on detection of such symptoms. Of the UH-1H accidents that have occurred, complete failure of the drive shaft has typically occurred in just a few minutes leading to an emergency landing and significant damage to the helicopter. In addition, pilots should be aware that complete failure of the KAflex can unexpectedly lead to right yaw, which is contrary to indications of a loss of drive to the main rotor system detailed in the flight manual.
The ATSB also reminds UH-1H helicopter pilots, operators, and maintainers that fatigue cracking can occur on critical flight components. Particular vigilance should be applied during the daily or pre-flight inspections of the main transmission driveshaft because it represents an important opportunity to detect for defects such as cracks, and to identify evidence of loose or missing attachment hardware.
The occurrence
On 10 February 2022, a bushfire developed after a registered burn escaped containment lines near Pipers Brooke Road, north of Launceston, Tasmania (Figure 1). A multi-agency[1] response commenced work to contain the ‘Lebrina’ fire using fire tankers, bulldozers and helicopters performing aerial firebombing. The pilot of a Garlick Helicopters[2] UH-1H, registered VH-UHX, was tasked by the Tasmania Fire Service (TFS) to combat the fire, which by 13 February had burnt 1,662 hectares of bushland and forestry plantations.
Over the period 10–13 February 2022, the pilot flew multiple firebombing sorties over the fireground from a temporary staging area established by TFS on a private field adjacent to Pipers Brook Road. At the conclusion of each day’s activity the helicopter was flown to the south of Launceston and hangared at the pilot’s residence.
Figure 1: Accident location and the Lebrina fireground, Tasmania
Source: Google Earth, annotated by the ATSB
On 14 February 2022, at about 0833 local time, the pilot departed their residence in VH-UHX and tracked toward the staging area. They then completed firebombing operations in the north‑eastern sector of the fireground. The tasking involved flying circuits between the fire boundary and a nearby dam, where an underslung water bucket was replenished with water. After completing several sorties, the pilot returned to the staging area and landed, shutting down the helicopter at 0929. The pilot remained at the staging area with other helicopter pilots, ground support and firefighting personnel.
At about 1455, 2 fire commanders, a TFS observer, and a pilot departed the staging area in an AS350 helicopter, registered VH-RLR (designated Firebird 460), to provide air attack supervision and to conduct an aerial survey of the fireground. Shortly after 1500, the personnel onboard Firebird 460 observed a rising plume of smoke in a region of unburnt vegetation on the western flank of the fireground. In response, they requested a firebombing helicopter attend the spot fire.
The pilot received the TFS request and, at about 1509, departed the staging area in VH-UHX. Witnesses at the staging area observed VH-UHX proceed to a small dam and hover, while the pilot filled the underslung bucket with water. The helicopter then departed and climbed toward the designated target (Figure 2).
The pilot and TFS personnel within Firebird 460 observed VH-UHX approach the spot fire and the release of the water load from the underslung bucket. The pilot of Firebird 460 recounted that the drop was unusual because they estimated the water had missed the target by ‘hundreds of meters.’ VH-UHX then commenced a gradual climbing turn to the left and tracked to the north‑west. To avoid any potential conflict with the now‑approaching helicopter, the pilot of Firebird 460 initiated a climbing 360° right turn, with those onboard losing sight of VH-UHX during the manoeuvre.
After completing the turn and regaining sight of VH-UHX, the Firebird 460 pilot recalled that the helicopter was now beyond the bushland and above an open paddock. They then witnessed the underslung longline and bucket fall to the ground and the helicopter descend rapidly. The pilot commented that VH-UHX appeared to be ‘diving toward the paddock’, in what they assessed was preparation for an emergency landing. Noting that the airspeed and descent rate for VH-UHX had increased, the pilot in Firebird 460 did not identify any slowing or flaring as the helicopter approached the ground and commented that their attention was also diverted to finding a suitable nearby landing site to provide assistance.
A passenger onboard Firebird 460 recalled irregular side-to-side movement of the tail section and a brief puff of white smoke emanate from the rear area of VH-UHX as it descended, prior to it colliding with terrain. They further commented that there did not appear to be any dust or debris from rotor wash that would normally be expected as VH-UHX approached the ground. Further, the Firebird 460 pilot did not hear any radio calls from the pilot of VH-UHX following the approach to the spot fire.
About 30 seconds after the collision, the pilot of Firebird 460 landed adjacent to the wreckage and alighted along with the TFS personnel. They reported that VH-UHX was on its left side and substantially damaged. Small fires had ignited in the surrounding grass and within the engine bay. The responders from Firebird 460 were unable to suppress the fire using handheld fire extinguishers. A nearby witness attended the site and connected a strap between their vehicle and the right skid of VH-UHX, however the helicopter was unable to be moved. The fire spread quickly and within a few minutes the wreckage was engulfed.
Two other pilots who were positioned with their helicopters at the TFS staging area responded to the emergency and proceeded to the accident site. They deposited multiple loads of water, however the fire was unable to be extinguished. The pilot of VH-UHX sustained fatal injuries and the helicopter was destroyed.
Figure 2: Key areas of the Lebrina fireground relative to the accident site
Source: Google Earth, annotated by the ATSB
Context
Additional witness information
A pilot-witness positioned at the Tasmania Fire Service (TFS) staging area had been monitoring VH-UHX, described seeing the pilot depart in VH-UHX, fill the underslung bucket at a nearby dam and then track toward the spot fire. They further identified that the water drop was conducted too high and too early, significantly missing the target. The helicopter was then observed to slow and commence a descending profile before completely rotating twice to the right about its vertical axis (yawing). The helicopter then pitched up and then down, before rapidly descending with a nose‑low pitch attitude.
Personnel onboard the air attack supervising helicopter (Firebird 460) captured several images and a short video of VH-UHX approaching the designated spot fire. One of the images showed the early release of water from the underslung bucket (Figure 3). The video file recorded by another passenger commenced in the moments after the water had been released and showed VH-UHX in a left turn (Figure 4). The video did not capture the yawing movement reported by the pilot-witness at the TFS staging area.
Another witness who was in their house near to the accident site recalled seeing VH-UHX in a descending approach. In their statement the witness reported hearing a screeching/roaring noise, with the helicopter observed to be descending in a left banking turn before moving out of sight.
Figure 3: VH-UHX releasing the underslung bucket contents at a considerable height and distance away from the spot fire (smoke plume)
The image was captured by a witness onboard Firebird 460. Metadata identified that the image had been captured at timestamp 1514:42
Source: Rod Sweetnam
Figure 4: VH-UHX in a left turn moments after the water release
This image is cropped from a video file captured by TFS personnel within Firebird 460 and shows the empty underslung bucket trailing VH-UHX
Source: Tasmania Fire Service, modified by ATSB
Aircraft information
General
The UH-1H ‘Huey’ helicopter was developed by Bell Helicopters in the 1960s as a military utility helicopter for the United States (US) Army. Records showed that the accident helicopter was manufactured in November 1965 (airframe serial number 64-13865). After ceasing US Army operations, surplus UH-1H helicopters were made available for civilian operations. Several organisations were authorised by the US Federal Aviation Administration (FAA) to convert ex‑military helicopters for civilian use. This included Garlick Helicopters Inc, who was the type certificate holder for this helicopter.
Operational arrangements
In September 2014 the helicopter was listed on the Australian civil aircraft register as VH‑UHX. In October 2014, the Civil Aviation Safety Authority (CASA) issued a special certificate of airworthiness permitting the helicopter to be operated in the restricted category to complete agricultural, forest, wildlife conservation, firefighting, and slinging of external loads. An additional special certificate of airworthiness was issued by CASA in May 2015 for the purpose of conducting adventure flights.[3]
The helicopter was purchased by its last owner in July 2020 to complete firefighting and slinging contracts. A pre-purchase inspection report completed on VH-UHX prior to the sale identified no airworthiness issues. The owner entered a contractual arrangement with Richmond Valley Aviation to operate and maintain the helicopter. Richmond Valley Aviation was in turn contracted to the National Aviation Firefighting Centre to provide on-call aerial firefighting capability using VH‑UHX.
The pilot, who was based in Tasmania, was contracted by Richmond Valley Aviation. The helicopter was re‑positioned to Tasmania in early 2021 where it was operated solely by the accident pilot.
Fuel
A 4,400 litre fuel storage tank was located at the pilot’s property where VH-UHX was hangared. This tank was used to replenish two 1,325 litre fuel storage tanks and four 205 litre drums on a refuelling truck. It was reported that VH-UHX had used drum fuel from the refuelling truck for the entirety of the Lebrina fire campaign tasking.
On the morning of 14 February, VH-UHX was fuelled from the refuelling truck that had been positioned at the TFS staging area. Fuel records indicated that 124 litres were added to the main tank of the helicopter, bringing the total fuel onboard to approximately 700 litres at the time of the final departure.
A sample of this fuel was obtained from the truck. Testing showed the sample was clear and slightly straw-coloured with no visible contaminants or indication of water. A visual inspection of all the fuel storage tanks similarly revealed no visible contaminants.
Water bucket
For firebombing applications, the helicopter used either 1,200 or 1,400 litre flexible buckets. The bucket was attached to the helicopter cargo hook via a 150 ft steel cable (longline). A push button switch mounted on the collective control was electrically connected to an air‑operated valve within the bucket that allowed the pilot to regulate the water release, including complete dumping of the water.
Cargo hook
VH-UHX was fitted with an equipment cargo hook that allowed external cargo to be released via an electrical switch on the pilot’s cyclic control grip. A switch on the forward section of the overhead console enabled the system to be armed and/or isolated. In addition, a foot-activated manual release lever was located between the tail rotor pedals. This release lever was used to jettison cargo in the event of an emergency or failure of the electrical release system. The ATSB was informed that the pilot sometimes isolated electrical control for the cargo hook. With the cyclic switch inoperative, the foot-activated manual lever was the only available option to release the external cargo.
Wreckage and impact information
Accident site
The helicopter wreckage was located in a grassy paddock near Pipers Brook Road, about 2.6 km north of the TFS staging area. The helicopter had been destroyed from ground impact forces and the subsequent fuel-fed fire (Figure 5). A survey of the accident site showed the wreckage to be orientated in a westerly direction (Figure 6).
Ground marks at the site showed that the tubular steel tail skid on the underside of the tail boom first contacted the ground, followed by the landing skids, main rotor blades and the cabin. After the initial ground strike, almost the entire tail section, including the tail rotor gearbox, separated from the fuselage, coming to rest a short distance beyond the main wreckage. Other items that separated from the helicopter included both main rotor blades, the battery and the landing skids. Three distinct ground scars identified where the main rotor blades struck the ground.
Figure 5: View of the fuselage and separated tail section at the accident site
The Lebrina fireground was located beyond the foreground tree line at the perimeter of the paddock. The upper wire cutter guide, longline and water bucket were located further back toward the tree line.
Source: ATSB
Figure 6: Overhead view of the accident site
Source: ATSB
The furthest items from the accident site were the tip from the upper wire cutter guide (located 220 m from the wreckage) and the underslung water bucket that remained attached to its longline (located 300 m from the wreckage) (Figure 7). Deformation to the fractured wire cutter guide was consistent with it being struck and projected by a main rotor blade.
Figure 7: Accident site showing the flight track of VH-UHX (red/green shaded area) and items that had liberated from the helicopter
Source: Google Earth, modified by ATSB
Engine examination
The helicopter was fitted with a Lycoming T53-L-703 turboshaft engine. The T53-L-703 consists of a single-spool five-stage axial compressor with the sixth-stage being a centrifugal flow compressor. The high-pressure turbine (gas producer) drives the compressor and accessory gearbox, while the low-pressure turbine (power turbine) drives the output gearbox to the main transmission drive shaft.
Examination of the wreckage identified that the main support mounts and forward trunnion mounts to the engine were still connected, however the supporting tubular frame had torn from the engine bay floor area during the impact. The engine was significantly damaged by the post-impact fire, resulting in destruction to the electrical looms, braided oil lines and the accessory gearbox. The engine fuel filter was removed from the engine and was found to be clear with no visual contaminants.
The power turbine was unable to be rotated. However, metallic material had solidified at numerous locations on the second-stage power turbine aerofoil surfaces indicating that metallic debris had passed through the combustion chamber while the engine was operating. Although absolute engine power levels were not able to be assessed the extent of internal compressor damage in combination with the ingested debris provided evidence that the engine was rotating at high speed during the impact sequence (Figure 8).
Internal inspection[4] of the compressor section identified that the compressor blades had been dislodged and bent against their normal direction of rotation. Debris was found throughout the compressor, including a piece of the main transmission drive shaft (KAflex coupling), multiple blade segments, inlet guide vanes and pieces of airframe structure (Figure 9).
Figure 8: Solidified metallic deposits were identified on the surfaces of the second stage power turbine
Source: ATSB
Figure 9: Severe disruption occurred to all internal stages of the compressor (left) and the debris that was recovered from within the compressor (right)
The rectangular item in the right image is a piece from the main transmission drive shaft (KAflex) Source: ATSB
Flight controls
The UH-1H flight control system is hydraulically assisted and actuated by conventional helicopter controls for both the pilot and co-pilot. Due to the extensive fuel-fed post-impact fire, most of the aluminium flight control components were destroyed leaving behind the steel componentry and connecting hardware. Of the recovered connecting hardware there was no evidence of missing fasteners or disconnections.
Tail rotor control system
VH-UHX was fitted with composite tail rotor blades connected to a common yoke by a grip and pitch change bearings. The hub and blade assembly are mounted on the tail rotor shaft with a delta-hinge trunnion and a static stop to minimize rotor flapping. Heading control is accomplished by movement of the anti-torque pedals which are connected to the pitch control system through the tail rotor (90°) gearbox. A multi-segmented drive shaft provides power from the main transmission to a 42° gearbox then to the 90° tail rotor gearbox.
The tail rotor anti-torque pedals were partially identified; however, the majority of the system had been consumed by fire. Continuity to the extent possible was established through to the tail boom section. The tail rotor drive shaft displayed rotational scoring damage at various locations along its length. The composite tail rotor blades also displayed evidence of impact damage from a ground strike. The tail rotor gearbox had fractured through its mount at the end of the tail boom. There was no evidence of pre-existing damage to the separated tail rotor gearbox with no evidence of binding or internal seizure. Overstress features present on the gearbox mount fracture surfaces were consistent with ground impact.
Hydraulic system
The hydraulic system is used to minimise the force required by the pilot to move the cyclic, collective and pedal controls. Due to the extensive damage sustained to the helicopter from the post-impact fire, a detailed assessment of the hydraulic system components was not possible.
Fuel
Only partial remnants of a flexible fuel cell were identified within the wreckage. No fuel was recoverable from the aircraft for testing.
Transmission
The UH-1H main rotor transmission is mounted forward of the engine and connected to the power turbine shaft at the front end of the engine by the main transmission drive shaft (KAflex). A freewheeling unit (sprag clutch) within the transmission reduces drag on the main rotors following an engine power loss, enabling an autorotative landing.
The wreckage examination identified that the transmission had partially separated from its airframe mounts and was located on its left side. The mast had fractured during the impact sequence, liberating the rotor head and both main rotors. The freewheeling unit within the transmission housing was seized due to the extensive heat damage from the post-impact fire and unable to be moved. The post-impact fire consumed a large section of the transmission housing exposing the main bull gear. There was no observable pre-impact damage to the gear teeth.
Main transmission drive shaft
The main transmission drive shaft (KAflex) was identified at the accident site to have fractured into multiple pieces (Figure 10). One of those pieces was found within the compressor section of the engine. Due to the extent of impact and fire damage, several attachment bolts and portions of flexible frame elements from the coupling were unrecoverable. The KAflex components were retained for subsequent examination at the ATSB’s technical facilities in Canberra.
Figure 10: Burnt wreckage noting the forward section of the fragmented KAflex main transmission drive shaft
Source: ATSB
Recorded information
Flight data recorders
The helicopter was not fitted with a flight data recorder or cockpit voice recorder, nor was it required to be.[5]
GPS and other data
The helicopter was equipped with a Tracplus tracking system that recorded GPS positional information at 2-minute intervals. Due to the relatively low sampling rate, the Tracplus data provided general aircraft track information rather than high fidelity information about the accident flight. The Tracplus data identified that for the accident flight, the system had commenced recording at 1508:49, which corresponded with the pilot preparing to depart from the TFS staging area.
A Garmin 296 GPS system was recovered from the accident site. The GPS was retained by the ATSB for data recovery at the ATSB’s technical facilities in Canberra. The device recorded time, position, ground speed and barometric altitude at varying time intervals, ranging between 1‑15 seconds.
Those onboard the Firebird 460, also recorded imagery and video files throughout the flight. Data from those files provided timestamp and georeferenced information. The ATSB completed an analysis of the available recorded data during the accident flight (Figures 11 - 13).
Take-off, water pick-up and climb out
At about 1509, VH-UHX departed the staging area and proceeded to a dam approximately 1 km to the west. At 1512:50, the helicopter was slowed to a hover, indicating the underslung bucket was being filled with water. After about 30 seconds overhead the dam, the helicopter departed and climbed to an altitude of 1,100 ft above mean sea level (AMSL) while transiting to the spot fire.
Water drop
At 1514:11, a left descending turn was conducted toward the spot fire at an average descent rate of about 250 ft per minute. During this time, the helicopter was slowed from a ground speed of about 60 kt to 30 kt. An image taken at 1514:42 by a TFS member onboard Firebird 460 showed water being released from the underslung bucket. GPS data indicated that VH-UHX climbed about 30 feet around that time, consistent with the reducing weight of the underslung load.
Cruise descent, deceleration, and final climb
From 1514:52 to 1515:22 VH-UHX descended at an average rate of 400 feet per minute to an altitude of about 780 ft AMSL, while slowing from about 68 to 55 knots ground speed. The ground speed and the rate of descent of about 400 feet per minute indicated that this was a powered descent, based on the autorotational glide characteristics from the UH-1H helicopter flight manual. Based on the data, about 20 seconds into the descent, VH-UHX was established over open terrain.
Following this, UHX commenced a shallow climb up to an altitude of about 840 feet, with the track changing by about 20° to the right, and the ground speed reducing to about 36 knots. The data did not contain sufficient information to determine the rate of yaw or the pitching movements observed by the pilot-witness at the TFS staging area.
It was not possible to determine the precise location of the helicopter when the bucket was released. However, based on the recorded flight path and the location of the bucket, approximately 300 m to the east of the main wreckage, the ATSB estimated the earliest possible release point of the bucket was at 1515:31, when the helicopter was in a slight climb and the track had altered slightly to the right.
Recorded rapid descent
The final 2 data points (Figure 13) indicated that VH-UHX descended at a mean rate between 1,500 and 1,700 feet per minute, consistent with autorotation. Calculations indicated that the descent commenced at approximately 430 ft above the terrain. During this time, the horizontal ground speed component of the helicopter initially reduced to about 30 kt before increasing to about 50 kt. The final data point from the onboard GPS was recorded at 1515:45. The final data point from the Tracplus was transmitted at 1515:58 and was likely a post-collision system shutdown.
Figure 11: Garmin 296 track data showing the flight path of UHX during the accident flight
Source: Google Earth, annotated by ATSB
Figure 12: Presentation of recorded data plotting altitude and groundspeed against local time
Key moments in the accident flight sequence of events are annotated
Source: ATSB
Figure 13: Presentation of the final GPS data points from the accident flight plotting altitude and ground speed against local time
Source: ATSB
Aircraft performance
Weight and balance
The ATSB evaluated whether VH-UHX was operated within the allowable weight and balance limits during the accident flight. Weights considered for this assessment included the onboard equipment, approximately 700 litres of fuel, pilot weight, and the weight of water contained within the bucket. A load cell and onboard digital gauge allowed the amount of water in the bucket to be monitored and provided a means for the pilot to assure that the helicopter remained within weight limits.
Although it was not possible to determine the precise amount of water transferred into the bucket from the dam, the ATSB concluded that VH-UHX was likely operating below the maximum take-off weight and within the centre of gravity limits throughout the accident flight.
Emergency procedures
Total power loss vs drive shaft failure
Emergency procedures were described in Chapter 9 of the UH-1H Operator’s Manual. For an engine malfunction or complete power loss, the manual stated that:
a. The indications of an engine malfunction, either a partial or a complete power loss are left yaw, drop in engine rpm, drop in rotor rpm, low rpm audio alarm, illumination of the rpm warning light, change in engine noise.
Additionally, the manual detailed the following indications associated with a drive shaft failure:
A failure of the main driveshaft will be indicated by a left yaw (this is caused by the drop in torque applied to the main rotor), increase in engine rpm, decrease in rotor rpm, low rpm audio alarm (unmodified system), and illumination of the rpm warning light. This condition will result in complete loss of power to the rotor and a possible engine overspeed. If a failure occurs:
1. Autorotate.
2. EMER SHUTDOWN.
Comparing the 2 malfunctions, in the event of a drive shaft failure the helicopter will exhibit some of the symptoms listed above for an engine power loss. Specifically, reduction in rotor RPM, activation of the low RPM audio alarm and illumination of the warning light would be expected. However, there will be no drop in engine RPM. Rather the engine RPM will likely initially increase (with associated noise), due to the sudden unloading from the rotor system.
Contrary to the advice in the Operator’s Manual, in both this occurrence and a past occurrence involving failure of the drive shaft (see the section titled Other occurrences), the helicopter unexpectedly experienced right yaw.
The helicopter manufacturer advised the ATSB that if the transmission RPM decreased, both the main rotor and tail rotor RPM would also decrease. A decrease in tail rotor RPM would result in less tail rotor thrust and therefore a nose-right yaw could occur. They further advised that a reduction in main rotor RPM would result in a corresponding reduction in hydraulic system pressure, which may then result in increasing stiffness through the flight controls (including the hydraulically boosted pedals). An overcontrol application of right pedal could occur due to these changes in control feel.
Forced landing
A successful forced landing in a single-engine helicopter can only be achieved if the helicopter has sufficient energy in the rotor to achieve the required landing deceleration and touch down configuration. For single-engine helicopters, the height-velocity (H/V) diagram is established by the manufacturer at the time of certification. The diagram:
defines an envelope of airspeed and height above the ground from which a safe power-off or one engine inoperative (OEI) landing cannot be made (FAA,2014).
The UH-1H flight manual included the H/V diagram for UH-1H helicopters, including VH-UHX (Figure 14). When operating at low speed in the shaded (or ‘avoid’) area on the left side of the diagram, in the event of a power loss, a pilot may have insufficient height to accelerate to the speed required to autorotate successfully. Above a certain height above the ground, at least 500 ft for the UH-1H depending on the density altitude, it is possible for a pilot to achieve autorotation speed even from a high hover. In the shaded area on the lower right side of the diagram, the combination of faster airspeed and proximity to the ground provides limited reaction time for the pilot in the event of an engine power loss. The FAA Helicopter Flying Handbook (FAA, 2019), stated:
…the shaded areas should be avoided, as the pilot may be unable to complete an autorotation landing without damage.
The unshaded region of the diagram shows the combinations of airspeed and height above the ground that allows a pilot to successfully complete a landing in a full autorotation without requiring exceptional skill. At low heights (below about 10 ft) with low airspeed, such as a hover taxi, the helicopter is in a safe part of the H/V diagram. There, a pilot can use the kinetic energy from the rotor disc to cushion the landing with collective, converting rotational inertia to lift. An increase in height without a corresponding increase in airspeed puts the helicopter above a survivable un‑cushioned impact height, until a height is reached from which rotor inertia and gravitational potential energy can be converted to sufficient lift to reduce the vertical velocity at impact to a survivable value (FAA, 2019).
The US Federal Aviation Administration (2019) also stated that:
As the airspeed increases without an increase in height, there comes a point at which the pilot’s reaction time would be insufficient to react with a flare in time to prevent a high speed, and thus probably fatal, ground impact.
The ATSB evaluated the likelihood that VH-UHX should have been able to complete a safe landing after an engine failure. Figure 14 and Figure 15 show the recorded heights and speeds of the last 6 data points from the flight path data. This shows that for this phase of the flight, the helicopter was outside the avoid area of the height-velocity curve, indicating that an autorotative glide should have been possible with the nominal helicopter rotor rpm.
Figure 14: Data points from the onboard GPS noting time, airspeed (calculated) and height are overlaid on the UH-1H height-velocity helicopter performance diagram
Source: Garlick Helicopters, annotated by the ATSB
Figure 15: The final data points from Figure 14 are overlaid against the final track of the helicopter
The approximate position of the yawing (rotations), the longline and fire bucket, and the accident site are also shown.
Source: Google Earth, annotated by the ATSB
Autorotative glide
The ATSB evaluated the descent of VH-UHX between the final recorded data points and the accident site for the purpose of establishing if it had entered a stable autorotative glide during the last part of the flight.
The calculated glide ratio from the last 2 flight data points was approximately 1 to 3.6, with a rate of descent of between 1,500 and 1,700 feet per minute and a ground speed of about 50 knots. Published UH-1H autorotational glide characteristics indicated that for an airspeed comparable to 50 knots and main rotor rpm of 314 rpm, a glide ratio of 1 to 3.8 is predicted at a descent rate of 1,600 feet per minute. The actual main rotor rpm was not recorded in the flight data and could not be determined. Further, there were insufficient flight data points to establish if the flight had entered a steady descent at this stage. Therefore, although the actual and published glide characteristics appeared to be comparable for this phase of flight, it was not possible to determine if VH-UHX was in a stable autorotation at the nominal rpm at this point in the flight.
A 1 to 1 glide ratio was estimated between the final recorded flight data point and the initial ground impact location. This ratio was at least 3 times steeper than that indicated by the flight data and published glide characteristics predicted for a stable autorotation noted above. This is consistent with the actual aircraft track, ground speed and vertical trajectory being considerably different to the last 2 flight data points. The most likely explanation for this is that the vertical speed was increasing between the final data point and the collision with terrain.
Personnel information
General
The pilot was an Australian citizen who had flown in several countries and had experience on numerous helicopter types. The pilot held a current commercial pilot licence (helicopter) that was issued on 22 December 2000, and a current Class 1 aviation medical certificate. In addition, the pilot held a low-level operational rating issued on 5 January 2001, with endorsements for helicopter sling-load operations issued on 21 June 2004. All the flight ratings held by the pilot were current and valid at the time of the accident and the pilot had worked with the TFS for several years.
Flying experience
Their logbook showed an accumulation of more than 9,900 hours total aeronautical experience, mostly in helicopters. In the previous 30 and 90 days, the pilot had flown 75 and 146 hours respectively and almost all those hours were accumulated in the accident aircraft.
The pilot attained a type rating for the UH-1H, in addition to the Bell 204 and Bell 205, on 9 July 2014. At the time of the accident the pilot’s total flying experience on the Bell 204, Bell 205 and the UH-1H was approximately 814 hours.
The pilot had about 2,090 hours total experience in aerial firefighting. In the last 90 days, most of the flying performed by the pilot (132 of the 146 hours) related to firefighting activities in the accident aircraft, with 108 hours of firefighting sling load operations recorded.
Proficiency
The pilot’s most recent aircraft flight review was completed in a Bell 505 helicopter on 5 August 2021. The ATSB consulted the flight examiner from an earlier review[6] where the pilot completed their proficiency check in VH-UHX. For the longline operational component of the check, during which the pilot’s control of the aircraft was assessed, the examiner reported requiring the pilot to select a water source, collect the water in the fire bucket and choose a target.
When asked about the pilot’s management of abnormal and emergency situations, the examiner advised that autorotations were conducted at elevations of 500 ft and 1,000 ft. Simulated hydraulic or engine failures were conducted, as well as a jammed flight control (usually the left pedal).
In the event of an emergency, the examiner advised the ATSB that pilots were trained to ‘clean‑up’ the aircraft by jettisoning the longline and bucket. Though it was normal industry practise to release the bucket and longline during an in-flight emergency, the examiner advised that it was up to the pilot’s discretion when to complete that action.
At the conclusion of the proficiency check, the examiner recorded that the accident pilot was of a ‘high standard’ and had no concerns with the accident pilot managing an in-flight emergency.
Fatigue assessment
The ATSB assessed whether the pilot may have been fatigued at the time of the accident. The pilot’s start times, rest time available, accommodation, environmental factors and workload associated with the task were all reviewed.
From the evidence available, while there were some long days of firebombing leading up to the accident, based on the pilot’s sleep obtained and the hours worked on the day and during the 72 hours prior (Table 1), it is unlikely the pilot was experiencing a level of fatigue that would have affected their ability to safely operate the helicopter.
Table 1: 72-hour pilot history
Duty
11 February 2022
12 February 2022
13 February 2022
14 February 2022
Flight time
10
10
6.5
1.0
Duty time
11.5
10
11
6.5
Survival aspects
Medical and pathological information
Post-mortem and toxicology reports were reviewed by the ATSB, with no natural disease or apparent toxicology identified. The post-mortem report concluded that the cause of death was a combination of head and thermal injuries.
Pilot seating
A flight manual supplement allowing the pilot in command to conduct operations from the left seat during external load operations was located in the recovered flight manual. The pilot was known to operate the helicopter from the left seat during firebombing operations. The pilot was located by first responders within their seat harness on the left side of the helicopter and had been wearing a flight helmet and flight suit. The left seat was fitted with a four-point harness, however, first responders were unable to advise whether the shoulder harness had been in use. Due to the significant vertical and horizontal loads, the resulting compression of the fuselage, and the post‑impact fire, the accident was not survivable.
Meteorological information
Meteorological reports and a private weather station within 5 km of the accident site indicated clear sky and light to moderate wind conditions. The air temperature at the accident site was estimated to range between 25°C and 29°C.
A pilot who was situated at the TFS staging area at the time of the accident described the weather as light winds from the east-north-east or the north-east and to be suitable for the helicopter firebombing operations.
Helicopter maintenance information
General
The logbook statement for VH-UHX specified that it was to be maintained in accordance with the Garlick Helicopters Inc. Instructions for Continued Airworthiness (ICA) report GH-H13WE-CA1H. The Garlick ICA report stated that the UH-1H helicopter-type was to be maintained in accordance with the US Army technical publications.
The US Army UH-1H maintenance schedule included a phased program that had a 900-flight hour cycle with intermediate 150-hour phases. There were also 25-hour and daily inspections.
The special certificate of airworthiness for VH-UHX stated:
The helicopter must at all times be operated in accordance with the UH-1H TM-55-1520-2010-10 and any approved Flight Manual Supplements associated with FAA or CASA approved modifications to the aircraft.
Recent scheduled maintenance
The helicopter’s maintenance records identified that the helicopter had accrued 6,786 hours total time in service while operated in the US. The records further indicated that by 30 January 2022, the helicopter had accrued a total time in service of 7,746.0 hours.
A scheduled 150-hour airframe and engine inspection was conducted by Richmond Valley Aviation between 26–30 January 2022. An additional inspection of the engine’s axial compressor and stators was performed requiring the removal of the top half of the compressor case. The compressor was washed and a linear actuator for the compressor guide vanes was replaced. In addition, the helicopter’s KAflex main drive shaft was removed and inspected. No defects were detected.
On 13 February 2022, the day prior to the accident, a scheduled 25-hour inspection that included a main rotor blade examination and airframe lubrication was completed by a licensed maintenance engineer at the pilot’s residence. The engineer recalled that no defects were identified during the inspection.
A partly burnt maintenance release was recovered from the wreckage. The document was issued on 30 January 2022 with an expiry of 30 January 2023, or 150 hours of operation from the time of issue, whichever occurred first. A signed entry on the document indicated that the daily inspection had been completed on 14 February 2022. There were no endorsements (defects) annotated on the maintenance release.
Flight time from 30 January 2022 was unable to be established due to fire damage. However, examination of the pilot’s flight records established that the helicopter had operated for 38 hours since the 150-hour phased inspection.
Unscheduled maintenance
In December 2021, while the pilot was completing firefighting operations at Sisters Beach, Tasmania, a defect associated with the 90° tail rotor gearbox was detected by the pilot. An attaching stud had reportedly loosened and contacted the upper part of the tail rotor drive shaft clamp. The helicopter was grounded until the gearbox and several components from the tail rotor drive system were replaced.
Richmond Valley Aviation reported that the KAflex drive shaft was scheduled for replacement due to the release of Federal Aviation Administration airworthiness directive (FAA AD) 2021-26-16, which became effective on 25 February 2022. The operator’s maintenance personnel advised that they had discussed the replacement of the KAflex with another type of greaseable drive shaft with the pilot and scheduled the replacement for the end of February 2022.
KAflex – main transmission drive shaft
General description
The KAflex main drive shaft for the UH-1H was manufactured by Kamatics Corporation (Kamatics). It was initially manufactured for the US Army in 1975 and was utilised as a direct replacement for the original Bell Helicopters driveshaft in their UH-1H fleet. The KAflex drive shaft is a flexible mechanical assembly that transmits torque from the engine output shaft to the input quill of the main rotor transmission. The drive shaft uses plates (flex frames) to accommodate relative movement between the engine and transmission. In normal operation, each flex frame transmits load from one bolt pair to the next bolt pair (Figure 16).
The drive shaft is designed with a fail-safe feature. Should an in-service fracture occur within the flex frame pack, or in the attaching hardware, the interconnect and end fitting are forced together. The resultant friction maintains drive between the engine and transmission. The off-centre and out-of-balance operation of the interconnect shaft causes vibrations, which signals that a partial failure has occurred and fail-safe mode is in operation (Figure 17). A pilot may be alerted to a shaft operating in fail-safe mode by increased noise and vibration.
Kamatics advised the ATSB that during qualification testing to demonstrate the fail-safe feature, a drive shaft demonstrated 21.5 minutes of continued powered operation when a flex-frame had been intentionally failed. The testing involved a short-term high-power operation (such as a climb or to manoeuvre to avoid an obstacle) followed by reduced power operation (such as flight in search of a landing site).
The testing did not consider a bolt failure and Kamatics advised a rapid decline of the shaft would result if a bolt failure were to occur.
KAflex maintenance
Kamatics reported that the US Army developed their own technical manuals and instructions for continued airworthiness for maintaining the KAflex drive shaft. It was to be inspected daily (pre‑flight) and during the phased-maintenance intervals. No life-limits were applied by the US Army to the drive shaft.
The US Army phased maintenance required the KAflex to be visually inspected after every 150 hours of operation. Specifically, the instructions listed the following statement and required maintainers to:
CAUTION: Do not attempt to loosen or tighten any hardware. Any reason for necessary part removal is cause for shaft replacement.
a. Visually inspect shaft for cracks.
b. Visually inspect shaft for nicks, dents, scratches and corrosion.
(1) superficial scratches
(2) damage to protective coating.
The 150-hour inspection did not explicitly state to check for red metallic residue or debris at the bolted connections. Kamatics advised that a check for fretting material could be an early indicator of a washer failure or joint movement from loose bolts.
The daily inspections were to be completed by the pilot and were listed in the operating procedures and manoeuvres section of the UH-1H flight manual.[7] The VH-UHX flight manual recovered from the accident site was severely damaged. It had been partially burned, and was fuel and water soaked, and was therefore incomplete. An exemplar flight manual was sourced that advised:
Main driveshaft – Check condition and security.
Figure 16: KAflex main transmission drive shaft
The main components of the drive shaft and their quantity are labelled
Source: CASA, annotated by the ATSB
Figure 17: KAflex – normal operation and fail-safe mode
Source: Kamatics Corporation, annotated by the ATSB
KAflex drive shaft part history
Component records for the drive shaft, serial number 0110, were provided by the manufacturer and showed that the KAflex (fitted to VH-UHX) had been released into service in 1978 as part number SKCP2180-1 to be operated and maintained by the US Army. The records further showed that in 1979, it had been returned to Kamatics for disassembly and the connecting hardware was changed over, being released as updated part number SKCP2281-103.
Throughout its history installed within the UH-1H helicopter, there was no specified life-limit or a time-between-overhaul for the KAflex. The shafts were operated and maintained on-condition and this maintenance practice continued when UH-1H helicopters were transferred to the civil register.
The maintenance organisation reported that the drive shaft hours had not been tracked because of the on-condition requirements associated with its service life. The KAflex was removed during the last scheduled phased inspection, approximately 39 hours prior to the accident. During that period of maintenance, the shaft was visually inspected prior to reinstallation into VH-UHX with no identified defects.
United States Federal Aviation Administration airworthiness directive
In 2018, Kamatics reported to the FAA their concern over several KAflex drive shaft failures that had occurred within UH-1H civil-operated helicopters. They identified that several variants of the KAflex were in extended use and had an unknown period of service. Prompted by those safety concerns, on 21 January 2022 the Federal Aviation Administration (FAA) issued airworthiness directive (AD) 2021-26-16, which became effective on 25 February 2022. The FAA AD advised that, if not addressed, an unsafe condition could result in the loss of engine power to the transmission and a subsequent loss of control of the helicopter.
The FAA AD required for operators to check the part number[8] and the total hours time-in-service of fitted drive shafts. A life-limit of 5,000 hours was also introduced by the FAA AD. If the drive shaft hours were unable to be verified through the maintenance records, the FAA AD required helicopter airframe total hours to be used as a measure of the overall drive shaft service life.
The FAA AD instructed that KAflex drive shafts with less than 5,000 hours service were able to be overhauled in accordance with FAA approved procedures. Additionally, shafts were to be removed from service if during visual inspection the following damage was identified:
broken, loose or missing hardware
bolt movement
fretting corrosion and fretting product
mechanical damage, nicks, indents or corrosion.
Examination of the KAflex from VH-UHX
A detailed metallurgical examination of the failed KAflex was completed at the ATSB’s technical facilities in Canberra. The drive shaft had fragmented into multiple pieces (Figure 18). The end fittings had remained attached to the engine and transmission, respectively, with the separated interconnect tube and fractured pieces of flex frame recovered from the burnt wreckage. As previously indicated, one of the flex frame segments was found in the compressor section of the engine. Several flex frame segments were unable to be located at the accident site.
The intense heat damage sustained from the post-accident fire consumed evidence of markings usually present on KAflex drive shafts, including a factory-applied serial number (ink-stamped onto each end fitting), and the factory-applied torque stripe (for each assembled nut and bolt). A permanent mechanical stamping onto the interconnect ‘SER NO 0110’ identified the drive shaft serial number, confirming its 1978 year of manufacture.
Visual examination of the interconnect identified a portion at the end of the tube that had fractured with associated bell-mouth deformation. The fracture occurred where the transmission end fitting had resided during operation. A lip of material at the end of the interconnect tube had been rolled outward and the fracture surfaces smoothed, likely from sustained metal-to-metal frictional contact. The portion of the end fitting that resided within interconnect exhibited associated severe frictional damage to the shouldered portion of the coupling region (Figure 19). The ATSB noted the distinct similarity between this and other KAflex shafts that had entered fail-safe mode.
Kamatics technical data showed that the attachment hardware comprising the bolts, countersunk washers and the spacers were of the correct type for KAflex part number KCP2281-103. From that data it was established that of the recovered fragments there was 1 missing bolt from the engine portion of the drive shaft, and 3 missing bolts (and their nuts and washers) from the transmission portion of the drive shaft. Breakaway torque values were measured during disassembly of the KAflex for all remaining fasteners. None were shown to meet the assembly specifications, though it was identified that shaft had fragmented and had been exposed to a significant fire.
An additional missing washer from the transmission portion of the drive shaft was identified on an intact attachment bolt associated with a fractured flex frame (Figure 20). A red-coloured substance consistent with fretting product remained on the surfaces of the attachment bolt (associated with the missing washer) and the surrounding flex frame surfaces. Furthermore, 6 other countersunk washers had either radially cracked, or contained circumferential cracks (Figure 21). A metallurgical cross-section through one of the washers showed that angular cracks had initiated at the washer metallic coating, which had then penetrated into the steel substrate.
Detailed examination of the flex frame fracture surfaces was completed using an optical microscope and scanning electron microscope. Evident thermal damage to the surfaces of the damaged flex frames significantly damaged and/or obscured any possible fractographic evidence of the mechanism of failure. Similar thermal damage had occurred to washer / spacer attachment hardware. Many of the finer surface features on the flex frame fractures were completely or partially obscured from that thermal damage.
The results of ATSB’s technical examination were presented to Kamatics, the US National Transportation Safety Board, CASA and the operator’s maintenance personnel. Kamatics advised that the frictional damage sustained to the end fitting and corresponding fracture of the interconnect indicated that the shaft had entered fail-safe mode during operation.
Figure 18: KAflex prior to disassembly at the ATSB’s technical facilities
Not all flex frame fragments or their attachment hardware were recovered at the accident site. One flex frame fragment was found in the compressor section of the engine.
Source: ATSB
Figure 19: Photographic montage of the KAflex showing damage sustained upon entering fail-safe mode
The identification of severe frictional damage and fracture that had occurred to both the interconnect and the end fitting (transmission) indicated the shaft had entered fail-safe mode
Source: ATSB
Figure 20: Photographic montage identifying a missing washer and evidence of fretting product on the associated flex frame and its attachment hardware
Source: ATSB
Figure 21: Photographic montage of cracks (arrowed) in countersunk washers from the KAlex attachment hardware
The intact washer (left image) displaying a series of cracks (arrowed) was recovered from the flex frame shown at Figure 20
Source: ATSB
Other occurrences
The ATSB identified one occurrence in Australia and 6 in the US with similarities to this accident. Further details of the publicly available accident reports of these occurrences are contained at Appendix A of this report. In all cases, the fail-safe feature of the drive shaft performed as designed after fracture of a flex frame or attachment bolt, allowing continuous operation under load and time for the pilot to commence an emergency landing. Excluding VH‑UHX, the other accidents were non-fatal, however significant damage was sustained during some of the forced landings. To summarise:
Pilots became aware of a drive system problem due to increased noise i.e. a ‘howling’ or ‘shrieking’ sound and vibrations from the transmission area.
Once the main drive shaft has failed, stiffness through the flight controls may occur.
Once in fail-safe mode KAflex drive shafts transmitted operational power for just a few minutes, which was significantly less than the 21.5 minutes established during the Kamatics qualification testing (with the caveat that the testing did not consider a bolt failure and the associated rapid decline in the shaft).
Failures of the KAflex drive shafts were initiated by the fatigue cracking and eventual fracture of a flex frame, with a single reported instance of an attachment bolt fatigue fracture.
In each case, unique and deteriorating contact damage occurred to the interconnect and end fitting surfaces once the drive shaft entered fail-safe mode (Figure 22).
There was one other reported instance of a rapid nose-right yaw (rotation of the helicopter about its vertical axis), and associated loss of directional control prior to impact with the terrain, following the subsequent total failure of the drive shaft. That accident is documented in ATSB investigation AO-2019-070 and is also further discussed in Appendix A of this report.
The contributing factors that have been established from the investigation of other KAflex failures included:
unauthorised / inappropriate overhaul methods
operation with sustained misalignment of the helicopter drive system
drive shaft components being out-of-tolerance
high-frequency utilisation and heavy lifting operations
excessive wear due to loose attachment hardware (i.e. bolts).
Figure 22: A KAflex that entered fail-safe mode due to fatigue cracking of a flex frame element
Physical characteristics of fail-safe mode after complete failure of the drive shaft include severe frictional damage and bell-mouth (opening) deformation to the end fitting, along with associated frictional damage, deformation and eventual fracture of the interconnect.
Source: Kamatics Corporation
Safety analysis
Introduction
On 14 February 2022, the pilot of a Garlick UH-1H helicopter was supporting the Tasmania Fire Service (TFS) by providing aerial firebombing support to the Lebrina bushfire, northern Tasmania. At 1509 the pilot departed the local TFS staging area to extinguish a small spot fire in a region of unburnt vegetation on the western flank of the fireground. The helicopter was observed to unexpectedly miss the designated target with the underslung water load. It was then tracked toward an open paddock, losing directional control as it was slowed on approach to the paddock, before pitching steeply nose-down and colliding with terrain.
The following analysis details the factors that prevented the skilled and experienced pilot from conducting a survivable descent and landing.
Technical failure
The ATSB considered possible reasons for the apparent premature release of water from the underslung bucket during the accident flight, which was captured in imagery by personnel onboard a nearby helicopter. Two eyewitnesses, who knew the accident pilot and also conducted aerial firefighting operations, observed the release of the water from an elevated height. Based on their knowledge of the operation and the accident pilot, who was well-regarded for precision water bombing operations, they considered that the off-target release of the water was unlikely to have been accidental.
Technical examination of the KAflex drive shaft identified definitive evidence of the disruption and disconnection of the KAflex coupling that transmitted engine drive torque to the transmission. Further, this disruption was characteristic with a torsional-induced breakout of the transmission‑side interconnect tube and the end fitting. Metallurgical evidence of high contact forces and severe surface friction damage was identified on both transmission coupling and the interconnect bore. This failure mode typically results from fatigue cracking and fracture of an interconnected flex frame or attachment bolt.
Of significance in this occurrence was the presence of fretting product (oxide dust/deposits) over a frame joint at the transmission coupling, together with extensive wear to the plain shank of the associated frame bolt. The attaching bolt was found to be intact but missing one of the washers. It is uncertain when the washer separated, however the presence of the fretting product indicated the flex frame joint at that location had been unstable for a significant period of operation.
The effects of post‑impact fire on the surfaces of the recovered flex frames significantly damaged and/or obscured any possible fractographic evidence of the mechanism of failure. Despite this, the extent of physical evidence around the general failure of the coupling was sufficient to conclude that the shaft had partially failed and entered fail-safe mode.
Considering pilot accounts from previously investigated occurrences, although drive is initially maintained when a KAflex enters fail-safe mode, this malfunction results in significant noise and increased vibration. It was therefore considered likely that the early water release while on approach to the spot fire and the diversion toward clear ground were deliberate actions taken by the pilot in response to activation of the fail-safe mode.
Emergency management
Analysis of the recorded flight data confirmed that, following the water release, an initial powered descent was conducted by the accident pilot toward the open field. However, the analysis also indicated that, as the helicopter was slowed and gently climbed over the open area, complete failure of the KAflex occurred. This resulted in an instantaneous and complete loss of drive to the rotor system. At that time, the helicopter was outside of the avoid area of the height-velocity envelope, indicating that a successful forced landing should have been possible. As the outcome was significantly more severe, the ATSB considered the factors that hampered management of the emergency.
Based on the observations of a pilot positioned at the staging area, the loss of drive to the rotor system was accompanied by an abrupt and significant right yaw. That direction of movement was consistent with the described helicopter behaviour following a previous KAflex drive shaft failure, but contrary to the expected left yaw detailed in the Flight Manual. This indicated that the reduction in rotor RPM following the sudden loss of drive may have disproportionately reduced tail rotor thrust.
In addition, Bell Helicopter reported that as the main transmission slowed, reduced pressure from the hydraulic system would lead to a stiffening of the flight controls, increasing the potential for the pilot to over control the anti-torque pedals to the tail rotor. Alternatively, given their proximity, it is possible that debris from the failing KAflex may have impacted the flight controls and/or the tail rotor drive shaft, and affected their operation. The degree of fire damage prevented an assessment of whether that occurred.
Irrespective of the reason for the right yaw, it may have led to an inappropriate pilot response (at least initially), as uncommanded right yaw is generally associated with a loss of tail rotor thrust, due to either a related mechanical failure or an aerodynamic loss of tail rotor effectiveness.
In addition to any potential uncertainty created by the yaw direction, as the engine was still operating when the KAflex drive shaft decoupled, the pilot was likely presented with unusual indications of simultaneous declining rotor RPM and increasing engine RPM due to the sudden unloading of the transmission and rotor system. Additionally, it was reported that the pilot operated the helicopter with the electrical hook release system deactivated. Therefore, release of the bucket and longline could only be achieved via the foot‑activated pedal, which would probably have delayed the response to the unexpected yaw.
In combination, these factors would have presented the pilot with a significant challenge to both troubleshoot and respond to the emergency.
Analysis of the flight data showed that, during the reported rotations immediately following the failure of the KAflex, VH-UHX continued a shallow climb for an 8 second period. Consequently, as there was no drive being provided to the rotor system during this time, significant drag on the main rotor would have reduced the rotor RPM. The helicopter was then observed to abruptly pitch down (which may have further degraded the rotor RPM) and descend steeply. This was followed by recovery of directional control by the pilot.
Mistiming of collective input by the pilot during the termination and landing was considered unlikely given their flying experience and previous demonstration of competency in conducting autorotative approaches. Further, ground scars showed that the helicopter was oriented in a pitch up attitude and tracking straight, indicating the helicopter was flared by the pilot prior to impact.
The ATSB concluded that, possibly exacerbated by insufficient height, the pilot was unable to recover the low RPM state during the unpowered descent. This limited their ability to decelerate and arrest the descent of the helicopter during the emergency landing, leading to high impact forces, and the subsequent post-impact fire.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the collision with terrain involving Garlick Helicopters UH-1H, registered VH-UHX, that occurred 36 km north of Launceston, Tasmania on 14 February 2022.
Contributing factors
During the conduct of firebombing operations, the helicopter’s engine-to-transmission main KAflex drive shaft partially failed due to fracture of a flex frame attaching bolt, or a flex frame element and entered fail-safe mode. It is probable this resulted in the pilot jettisoning the water load from the underslung bucket and diverting toward clear ground.
As the helicopter was slowed during a descent over clear ground, the main drive shaft decoupled, probably at about the time the longline and underslung bucket were released. The failure resulted in an instantaneous loss of drive to the rotor system.
Following loss of drive to the main rotor system, the pilot was unable to complete a survivable autorotative descent and landing, probably due to a critical reduction in main rotor speed.
Safety issues and actions
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. All of the directly involved parties are invited to provide submissions to this draft report. As part of that process, each organisation is asked to communicate what safety actions, if any, they have carried out to reduce the risk associated with this type of occurrences in the future.
Whether or not the ATSB identifies safety issues in the course of an investigation, relevant organisations may proactively initiate safety action in order to reduce their safety risk. The ATSB has been advised of the following proactive safety action in response to this occurrence.
Proactive safety action taken by Civil Aviation Safety Authority
Action number:
AO-2022-006-PSA-01
Action organisation:
Civil Aviation Safety Authority
Action status:
Closed
CASA released Issue 3 to Airworthiness Bulletin (AWB) 63-004 Kamatics Corporation KAflex Drive Shafts – UH-1H and Bell 407, on 28 June 2022. The purpose of the AWB was to alert operators and maintainers:
That the approved Bell 407 Flight Manual did not adequately detail the pre-flight check inspection requirements with regard to checking the KAflex drive shaft for serviceability.
To alert operators of 2 ATSB investigations involving UH-1H helicopters where the KAflex drive shafts had failed (ATSB investigation number AO-2019-070 and AO-2022-006).
That the United States Federal Aviation Administration airworthiness directive AD 2021‑26-16 was applicable and imposed a 5,000 hour life-limit on the drive shaft.
Following review of the draft investigation report, on 5 March 2024, CASA released Issue 4 to AWB 63-004. Reflecting the advisory material contained in ATSB’s investigation report, Issue 4 of the AWB contained further advice to operators and maintainers on potential operational aspects once a KAflex has entered fail-safe mode.
Safety advisory notice to operators and maintainers of Garlick UH-1H helicopters
SAN number:
AO-2022-006-SAN-01
SAN release date:
15 June 2022
On 15 June 2022 the ATSB advised operators of UH-1H helicopters to note the details of this accident and to look for the presence of corrosion, fretting, frame cracking, missing or damaged attaching hardware during all inspections of the KAflex drive shaft. Any identified defects were to be notified to the Civil Aviation Safety Authority.
Additionally, operators should be aware of Kamatics’ concern of shaft serial numbers 0635 and below for the UH-1H helicopter that may be fitted with legacy attachment hardware. Kamatics should be contacted if a shaft in the affected serial number range is identified.
Proactive safety action taken by Tasmania Fire Service
Action number:
AO-2022-006-PSA-02
Action organisation:
Tasmania Fire Service
Action status:
Closed
The Tasmania Fire Service (TFS) advised that, since the accident, they have completed the following agency actions in relation to their aviation and emergency response operations:
TFS has transitioned to the Tasmanian Government Radio Network to enable direct communications with other emergency service organisations, fire land managers and aircraft operators working at multi-agency incidents.
In November 2022, TFS conducted an inter-agency training exercise to test the response to a rescue incident in remote and isolated areas. The exercise tested the TFS timelines, incident management command and control, communication links, processes and roles of each agency. A key outcome was that the notification procedures have been improved between TFS, Tasmania Police and the Ambulance Tasmania Air Rescue Aviation Unit.
Proactive safety action taken by Kamatics
Action number:
AO-2022-006-PSA-03
Action organisation:
Kamatics
Action status:
Closed
Kamatics advised that for KAflex shafts returned to their factory they will complete a teardown inspection to identify evidence of fretting, cracked washers or any other undesirable defect in hardware items normally replaced during overhaul.
Proactive safety action taken by Richmond Valley Aviation
Action number:
AO-2022-006-PSA-04
Action organisation:
Richmond Valley Aviation
Action status:
Closed
Richmond Valley Aviation, the maintainer and operator of VH-UHX, advised that subsequent to the accident they removed all KAflex drive shafts from service in aircraft that they maintained. Additionally, to mitigate the potential risk of future main transmission drive shaft failures they have elected to use an alternate type of drive shaft that has a 600 hour / 12-month inspection and re‑grease interval.
In their response they identified that the couplings of the alternate drive shafts have external temperature indicators that can provide a warning to pilots / maintainers of potential problems before they escalate.
Glossary
AD
airworthiness directive
AWB
airworthiness bulletin
CASA
Civil Aviation Safety Authority
CASR
Civil Aviation Safety Regulations
CVR
cockpit voice recorder
FAA
Federal Aviation Administration
FDR
flight data recorder
IAS
indicated airspeed
ICA
instructions for continued airworthiness
NSTB
National Transportation Safety Board
RPM
revolutions per minute
TFS
Tasmania Fire Service
Sources and submissions
Sources of information
The sources of information during the investigation included:
Richmond Valley Aviation
the helicopter owner and manufacturer
Kamatics Corporation
Bureau of Meteorology
United States Federal Aviation Administration and National Transportation Safety Board
Tasmania Fire Service
Civil Aviation Safety Authority
witnesses
the aircraft maintainer
the pilot’s flight examiner
onboard recorded GPS data.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
Richmond Valley Aviation
the helicopter owner and manufacturer
Kamatics Corporation
United States Federal Aviation Administration and National Transportation Safety Board
Tasmania Fire Service
Civil Aviation Safety Authority
the aircraft maintainer
the pilot’s flight examiner
witnesses
Submissions were received from:
Richmond Valley Aviation
the helicopter manufacturer
Kamatics Corporation
National Transportation Safety Board
Tasmania Fire Service
Civil Aviation Safety Authority
the pilot’s flight examiner
a witness.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Appendices
Appendix A: Related accidents and other investigations
During the course of this investigation, the ATSB became aware of similar accidents involving failure of KAflex main drive shafts. The United States (US) National Transportation Safety Board (NTSB) investigated and reported on 2 UH-1H accidents and the ATSB has previously investigated one other accident. Kamatics Corporation investigated 4 other failures and they can be contacted for details.
On June 3, 1997, a Garlick UH-1H helicopter, collided with the terrain during a forced landing near Addy, Washington. The commercial pilot, who was the sole occupant, was not injured, but the aircraft sustained substantial damage. According to the pilot, they were about 30 minutes into the first logging cycle of the day and heading back to pick up another log load when the accident sequence began. The pilot heard a high-speed shredding sound with accompanying high‑frequency vibration.
The pilot immediately lowered the collective and released the underslung 150 foot longline. While transiting away from tall forest trees the sound and vibration rapidly worsened. The pilot heard a second loud noise and identified that the main rotor RPM began to decay, prompting an emergency landing.
The NTSB found that a number of the flex frames on the drive shaft had failed. The KAflex was sent to the NTSB materials laboratory, and their metallurgical examination identified evidence of pre-existing fatigue cracking on the fracture surfaces of a flex frame.
NTSB accident number WPR15LA178
The pilot of a UH-1H helicopter reported that on 31 May 2015, while manoeuvring the helicopter at low altitude during logging operations, a vibration and howling sound was detected coming from the transmission area. In response, the pilot immediately initiated a precautionary landing, however, the flight controls stiffened as the helicopter settled to the ground and the main rotor RPM reduced. The helicopter landed heavily.
The NTSB materials laboratory found multiple fractures had occurred to the KAflex drive shaft assembly. The KAflex failure was initiated by the fatigue cracking and fracture of an attachment bolt that secured the coupling assembly to the transmission shaft flange (Figure A1). No evidence of any material anomalies were found in the fractured bolt.
Figure A1: The KAflex entered fail‑safe mode following fatigue fracture of an attachment bolt, prior to total failure of the drive shaft
The interconnect and end fitting displayed characteristic contact features from entering fail-safe mode
On 7 December 2019, the pilot of a UH-1H helicopter was completing fire control aerial work. While hovering and preparing to uplift river water into the underslung bucket, the pilot heard a momentary ‘burring’ noise with a ‘buzzing’ vibration through the airframe. The pilot aborted the uplift and started to transition away from the hover when the noise and vibrations resumed. The pilot noted the intensity increased when the collective lever was raised.
The pilot radioed the firefighting personnel of the intention to land, released the bucket and longline, and tracked towards a clear area. The continuing noise indicated to the pilot that the condition of the helicopter was deteriorating. In response, the pilot elected to divert to a small clearing. On approach to the hover, at a height of about 10 ft, the helicopter commenced an uncontrolled rotational yaw to the right, which the pilot was unable to stop. The helicopter rotated about 180° from the approach heading before landing hard.
The ATSB’s metallurgical examination found that the KAflex drive shaft had failed due to the development of a fatigue crack in a flex frame that led to its fracture prior to the hard landing (Figure A2).
Figure A2: Fatigue cracking of a flex frame element led to the shaft entering fail-safe mode prior to total failure during operation
The interconnect and end fitting displayed characteristic contact features from entering fail-safe mode
Source: ATSB
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1] Tasmania Fire Service, Sustainable Timber Tasmania, Parks and Wildlife Service, State Emergency Service and Reliance Forest Fibre responded to the fire.
[3] This type of flight uses a range of ex-military, historic and replica aircraft to offer adventure-style flights to the general public for a fee.
[4] The compressor section of the engine was examined using a flexible video borescope.
[5] Requirements relating to the fitment of flight recorders are detailed in Part 91 Manual of Standards (MOS), Division 26.9 Flight recording equipment.
[6] The proficiency check was completed on 11 December 2020.
[7] Department of the Army, Operator’s Manual, Army Model UH-1 H/V Helicopter, UH-1H TM-55-1520-210-10 section 8-19 Area 6 para 2.b
[8] Kamatics Corporation KAflex part number: SKCP2180-1, SKCP2281-1, SKCP2281-1R or SKCP2281-103
Preliminary report
Report release date: 29/04/2022
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
The pilot of a Garlick Helicopters UH-1H, registered VH-UHX, was tasked by the Tasmania Fire Service (TFS) to provide fire-fighting support to combat the ‘Labrina’ bushfire, centred approximately 34 km north of Launceston, Tasmania. Over the period 10‑13 February 2022, the pilot flew multiple aerial fire‑bombing operations over the fire-ground from a temporary staging area established along Pipers Brook Road. At the conclusion of each of these days the helicopter was flown to the south of Launceston and hangered at the pilot’s residence.
On 14 February 2022, at about 0833 Eastern Daylight‑saving Time,[1] the pilot departed toward the ‘Labrina’ fire-ground. Onboard GPS data showed that the helicopter tracked toward the staging area before diverting to the north-east sector of the fire-ground to conduct firebombing operations. Those operations were conducted using a water bucket attached underneath the cabin via a 140 ft long-line (the underslung bucket). After completing those sorties, the pilot returned to the staging area and landed, shutting down the helicopter at 0929.
At 1510, the pilot departed the staging area after receiving further tasking from TFS that a localised hot-spot had developed. The hot-spot had been identified by TFS fire commanders that were providing air attack supervision overhead the fire ground in an Airbus Helicopters AS350 helicopter, registered VH-RLR (designated Firebird 460). Onboard GPS data indicated that about 2 minutes after departure, VH-UHX entered a hover over a small dam where the pilot filled the underslung bucket.
Those onboard Firebird 460 observed VH-UHX approach the identified fire hot-spot and witnessed the release of the water load from the underslung bucket. The pilot of Firebird 460 recounted that the drop was unusual because the water missed the target (Figure 1). VH-UHX was then observed by those onboard Firebird 460 to commence a gradual left turn and track away from the staging area. Suspecting the pilot of VH-UHX was encountering an in-flight difficulty and wanting to avoid any potential conflict with the approaching helicopter, the pilot of Fireboard 460 initiated a climbing 360° turn away from VH-UHX.
A witness positioned at the staging area, who had also been monitoring VH-UHX, observed the pilot depart in the helicopter, fill the underslung bucket in a nearby dam and then track toward the hot-spot. On release of the water, the witness also identified that the load had missed the target. They then observed the helicopter commence a descending profile, enter a hover and then rapidly yaw twice, before descending from view below the tree line.
After completing the 360° turn the Firebird 460 pilot trailed VH-UHX and observed the helicopter descend toward an open paddock where it impacted the terrain. Throughout this monitoring phase, the Firebird 460 pilot did not detect any radio calls issued from VH-UHX. The Firebird 460 pilot landed adjacent to the wreckage and alighted along with the passengers to provide assistance. They reported that the helicopter was on its left side and was substantially damaged. A fuel-fed fire spread rapidly and despite attempts to extinguish the fire it was unable to be contained. Two other pilots who were positioned with their helicopters at the TFS staging area also responded to the emergency and proceeded to the accident site to supply aerial suppressant to the fire. The pilot of VH-UHX sustained fatal injuries and the helicopter was destroyed.
Figure 1: VH-UHX photographed by a witness onboard Firebird 460 completing the aerial water drop away from the identified hot-spot
Source: Rod Sweetnam, amended by ATSB
Wreckage and impact information
The helicopter wreckage was located in an open paddock near Pipers Brook Road, about 2.6 km north of the TFS staging area. It had been destroyed from exposure to ground impact forces and the subsequent fuel-fed fire. A survey of the accident site showed that the helicopter had impacted the ground along a westerly flight track. Ground scars at the site showed that the tail section made first contact with the ground, followed by the skids, main rotor blades and the cabin (Figure 2).
Almost the entire tail section, including the tail rotor gearbox, separated from the fuselage, and had come to rest a short distance from the main wreckage. Other items that separated from the helicopter included both main rotor blades, the battery and the landing skids. The furthest item from the accident site was the underslung bucket that remained attached to its long line. The bucket and line had been released from the helicopter prior to the ground impact and were positioned approximately 300 m from the wreckage.
Figure 2: Accident site
Source: ATSB
Aircraft information
The accident helicopter was manufactured as a UH-1H by Bell Helicopters in November 1965 for the United States (US) military and was converted by Garlic Helicopters for civilian application in November 2007 (Figure 3). The helicopter had a two-blade main rotor and two-blade tail rotor and was powered by a Honeywell Aerospace (formally Lycoming Engines) T53-L-703 turboshaft engine.
The helicopter was listed on the Australian Civil Aircraft Register as VH-UHX in September 2014. In October 2014, the Civil Aviation Safety Authority issued a Special Certificate of Airworthiness permitting the helicopter to be operated in the ‘restricted’ category for agricultural, forest, and wildlife conservation, firefighting, and slinging of external loads. An additional Special Certificate of Airworthiness was issued in May 2015 in the ‘limited’ category for the purpose of conducting adventure flights.
Maintenance records identified that the helicopter had accrued 6,785.6 hours total time in service while operating in the US. They further indicated that by 30 January 2022, the helicopter had accrued a total time in service of 7,746.0 hours.
Figure 3: VH-UHX at the Tasmania Fire Service staging area
Source: Jamie Davis
Recent maintenance
In December 2021, while completing fire-fighting operations at Sisters Beach, Tasmania, a defect associated with the 90° tail rotor gearbox required replacement of the gearbox and several components from the tail rotor drive system. Commencing 26 January and concluding 30 January 2022, a scheduled 150-hour airframe and engine inspection was conducted. An additional inspection of the engine’s axial compressor and its stator was performed that involved removal of the top half of the compressor case. On 13 February 2022, the day prior to the accident, a scheduled 25-hour main rotor blade inspection and airframe lubrication was completed at the pilot’s residence with no reported defects.
Further investigation
The investigation is continuing and will include consideration of the:
helicopter flight profile during the occurrence flight
engine, transmission, tail rotor gearbox and component examinations
witness reports, imagery and video footage
helicopter maintenance and its operational history
helicopter performance and emergency procedures
pilot’s qualifications, medical history, and experience
related occurrences in Australia and overseas.
An accredited representative from the US National Transportation Safety Board (NTSB) has been appointed to assist with the investigation.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Acknowledgements
The ATSB acknowledges the support of the Tasmania Police Force, Tasmania Fire Service, and all parties that assisted the investigation team through the evidence collection phase of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
On the morning of 19 December 2021, a Rockwell Commander 114, registered VH-WMM, departed Redcliffe aircraft landing area, Queensland for a private flight. On board were a pilot and 3 passengers. Shortly after take-off, the engine lost power and the pilot elected to return to the airfield. During the return, the aircraft lost altitude and impacted the ocean before becoming inverted. The occupants were unable to escape the aircraft and were fatally injured, and the aircraft was destroyed.
What the ATSB found
The ATSB found that during preparation for the flight, a perceived engine problem distracted the pilot during the conduct of pre-take-off checks. After rectifying the issue, the pilot did not complete the remaining pre-take-off checks (including fuel tank selection) before departure. Before take-off when there was no time pressure (and during the inflight emergency when there was), checks and action items were only done by memory rather than using the pilot operating handbook or third‑party checklists also on board.
While stored in the hangar, most of the fuel moved into the right wing tank. The pilot would have been aware of the fuel imbalance from measuring fuel in both tanks via a dipstick before flight. However, it was likely that the fuel tank selection prior to take-off was to the left fuel tank only, which led to fuel starvation and engine stoppage soon after take-off.
The pilot, likely experiencing the effects of stress and time pressure following the engine power reduction and then stoppage, did not conduct initial emergency actions and attempted to return to the runway for landing. However, the pilot did not maintain glide speed, and the aircraft impacted shallow water prior to reaching the airfield. During the return to the airfield, the pilot had extended the undercarriage for the intended landing. This contributed to the aircraft inverting when it collided with water. This likely resulted in occupant disorientation and added difficulty in operating the exits, reducing their ability to escape.
It is very likely that the passengers did not receive information about the brace position or actions to be taken in the event of a ditching as part of the pre-flight briefing. In the limited time available inflight after the power loss, the pilot also did not provide an emergency briefing or any instructions to passengers prior to impact with the water.
While the pilot was primarily responsible for the operation of the aircraft exits in an emergency, seating a child, who may require assistance, adjacent to an exit instead of an adult meant that a less suitable passenger was available to operate the exit.
Safety message
Use of the approved aircraft checklists, taken from the pilot operating handbook, provides pilots with the appropriate checks to be conducted for the aircraft type. Having these readily available in a written form, for the preparation and conduct of a flight, provides pilots with the detailed normal and emergency checks specific to the aircraft type without having to rely on committing these to memory. This ensures that aircraft are operated in a way that meets aircraft flight manual requirements and limitations.
Distraction can impact proper procedural processes and lead to interruption and omission of safety critical elements before take-off. The habit of restarting an interrupted checklist from the beginning is a means of ensuring that all steps to be performed are done so in order and the checklist is complete.
Thorough pre-flight briefings of passengers on how to operate exits, the brace position and actions that might be required in a ditching or other forced landing are essential to increase post‑impact survivability. Additionally, as supported by guidance, pilots should consider who might be best to assist in the case of an emergency, and brief and seat them accordingly.
Decisions regarding whether to conduct an investigation, and the scope of an investigation, are based on many factors, including the level of safety benefit likely to be obtained from an investigation. For this occurrence, a limited-scope investigation was conducted in order to produce a short investigation report, and allow for greater industry awareness of findings that affect safety and potential learning opportunities.
The occurrence
On the morning of 19 December 2021, at the Redcliffe aircraft landing area, Queensland, a Rockwell International 114 aircraft, registered VH‑WMM, was being prepared for a local private flight under visual flight rules.[1] On board for the flight were the pilot and 3 passengers. The weather conditions and visibility were good, with light winds from the east.
Closed circuit television (CCTV) showed the pilot conducting a pre-flight inspection of the aircraft. This included draining a small amount of fuel from each fuel tank drain to check for any water contamination and using a dipstick to check the fuel tank quantity of each tank.
A passenger video (seeAppendix - Sequence of events) was recovered from a mobile phone which showed portions of the taxi, before take-off checks, and the accident flight. Several witnesses at the airfield, in boats near the airfield, and in other aircraft also observed the flight of VH-WMM (Figure 1).
Before the take-off, passenger video showed the pilot conducting before take-off checks (from memory) and did not show the use of any written checklists. While conducting the engine run-ups, the pilot perceived a technical difficulty with the aircraft, and the checks were paused. After notifying a ground crew member by phone, the pilot taxied back toward the ground crew who was walking towards the aircraft on the taxiway. The ground crew member recalled that through hand signals, the pilot identified the issue as misidentification of the mixture control for the propeller pitch control and communicated that they had identified and corrected the problem.
The pilot then taxied again for runway 07 without continuing or restarting the interrupted before take-off checks and continued direct to the runway holding point. The occupants of VH-WMM then discussed where other traffic was in the circuit, before entering and backtracking to the end of the runway. VH-WMM then turned and commenced the take-off at 0908 local time.
After take-off from runway 07,[2] the aircraft’s undercarriage and flaps were retracted, and 62 seconds later, while in a left climbing turn, the engine RPM started to fluctuate, followed by a large drop in engine power 3 seconds later. The (adult) passenger, seated on the rear-right side of the aircraft then asked the pilot about fuel coming out of the top of the right wing; however, the pilot did not respond to the question. The video also did not indicate the pilot conducting any engine troubleshooting activities. The pilot made 2 further left turns, which were consistent with manoeuvring the aircraft back toward the western end of runway 07 (Figure 1), and the stall warning sounded twice. About 17 seconds after the power reduction (1 minute 31 seconds after take-off), the engine stopped.
Four seconds later, the video recorded the undercarriage warning bell followed by the stall warning. Based on the recorded sounds, it is likely the pilot responded by lowering the landing gear. Another pilot who was on final approach for runway 07 heard the pilot of VH-WMM broadcast on the radio that they were returning to the airfield.[3]
Figure 1: Redcliffe aircraft landing area and VH-WMM approximate flight path and accident site
Source: Google Earth, annotated by the ATSB
Over 24 seconds, the stall warning sounded another three times, followed by a turn directly toward the runway and then further stall warnings, two successive drops of the right wing and then the sounding of the ‘stall’ voice alert.
Three seconds later, as the aircraft neared the mangrove tree line to the north of the airfield, it contacted the water, about 170 m from the shoreline. The aircraft overturned and came to rest inverted in about 2 m of water.
The pilot of another aircraft that was inbound to Redcliffe who had also heard the pilot of VH‑WMM make the returning to the airfield call, was alerted to the possibility of an accident from an unknown person on the radio upon arrival. After observing an aircraft in the water, the pilot contacted Brisbane air traffic control (ATC) to advise them of the accident. The pilot remained overhead the accident site while boats arrived at the scene and continued relaying information to ATC.
Witnesses at the airfield and on nearby boats contacted emergency services and the Australian Volunteer Coast Guard. After being notified by a witness on a kayak, a nearby vessel made its way to the aircraft, arriving about 5 minutes after the accident. Following the impact with water, the inverted orientation of the aircraft meant that the door handles were submerged. First responders reported that it was difficult to locate the handles to open the doors from the outside. When inverted on the seabed in mud and silt, the upper door latches were also unable to be located. The disturbance of the mud/silt further reduced visibility of the exits and their operating handles.
A coast guard vessel arrived onsite; however, the crew were also unable to gain access into the aircraft’s cabin. Queensland Police Service divers arrived at the aircraft about 2 hours after the accident. They observed the water to be about 1.5 m deep. Upon entering the water, police observed that visibility was very poor. The pilot’s door was shut and could not be opened. The right door was unlocked and slightly ajar, and police were able to open the door with some difficulty. The pilot and 3 passengers were fatally injured, and the aircraft was destroyed.
Context
Pilot information
The pilot held a valid Private Pilot Licence (Aeroplane) and a Class 2 aviation medical certificate, valid until February 2023. The pilot held single and multi‑engine aeroplane ratings and endorsements for manual propeller pitch control, retractable undercarriage, and formation flying. At the time of the accident, the pilot had logged 334.3 hours in VH-WMM and had about 505 hours total aeronautical experience.
The flight instructor who conducted the pilot’s last flight review in July 2021 stated that the pilot was assessed on engine failure after take-off. They also described that the assessed procedures on that review were similar to the accident flight, insofar as location of engine power loss and the actions that were to be taken as a result. During the flight review, the pilot had performed all actions to a satisfactory level.
Pilot medical history
A review of the pilot’s Civil Aviation Safety Authority (CASA) medical file identified that the pilot had disclosed a hypertension condition and that they had been prescribed medication for it but did not list any other health issues or concerns.
Discussion with the pilot’s next-of-kin and general practitioner (GP) identified that the pilot was a long term, type 2 non-insulin dependent diabetic. The pilot had been prescribed medication for at least 10 years with medical records indicating tracked blood glucose readings back to January 2003, and an immediate family history of non-insulin dependent diabetes. The pilot had also been diagnosed with high cholesterol and had been prescribed medication for its treatment. The GP was also aware of a family history of heart disease.
Of the last 3 CASA aviation medical examinations, the pilot had not declared their high cholesterol, diabetic status, and diabetes medication to their CASA designated aviation medical examiner (DAME), however had disclosed family history of both diabetes and heart disease to the DAME. Regarding the question in relation to diabetes on the pilot’s pre-examination medical history, the pilot indicated ‘unsure’, which was later changed by the DAME to ‘no’ during the examination.
Toxicology reports showed that the pilot of VH-WMM had detectable quantities of several substances, including a prescribed medication, paracetamol, and an over-the-counter sedating antihistamine. A carbon monoxide concentration of less than 5% was also detected in the analysis.
The ATSB sought advice from a specialist toxicologist regarding the potential effects the detected substances may have had on the pilot during the accident flight. The advice indicated that the level of antihistamine detected in the samples was low and suggested the drug had been used between 12 and 24 hours prior to the accident. They also reported that although the medication the pilot had been prescribed may have increased the sedating effects of the antihistamine, given the low levels detected it was unlikely there was any significant impairment of the psychomotor skills[4] required to fly an aircraft.
The specialist toxicologist also identified that there may have been an interaction between the multiple antihypertensive medications that the pilot had been prescribed[5] to lower blood pressure. However, from the passenger video it was noted that the pilot did not appear to be physically incapacitated, so it is very unlikely the pilot experienced any form of incapacitation prior to the accident.
Aircraft information
General information
The Rockwell International 114 is a 4-seat, single-engine aeroplane with fully retractable, trailing link undercarriage. It is powered by a 6-cylinder Lycoming IO-540 fuel-injected engine and is fitted with a 3-blade constant-speed propeller. Passenger and pilot access is by a door on each side of the aircraft cabin (Figure 2).
VH-WMM was manufactured in the US in 1977 and was first registered in Australia in May 2013. The last periodic inspection was conducted on 7 July 2021. At the time of the accident, VH-WMM had accrued a total time in service of 3,431.4 hours and had flown about 11 hours since the last inspection.
Figure 2: VH-WMM
Source: Nathen Sieben, annotated by the ATSB
Fuel system
The Rockwell 114 fuel system consists of 2 integral (wet wing)[6] fuel tanks, 1 in each wing, with a fuel gauge for each tank located in the cockpit. The fuel capacity is 132.5 L for each tank, with 128 L considered usable. Both fuel tanks supplied the engine through the fuel selector, gascolator,[7] electric fuel pump and an engine driven fuel pump. The fuel selector valve had 5 positions, which allowed the pilot to select OFF, LEFT, BOTH, RIGHT and OFF positions.
The last refuelling of VH-WMM occurred before a flight on 16 October with an uplift of about 120 L of AVGAS, taking the total quantity to about full tanks. VH-WMM was then operated for about 2.2 hours over 2 flights, prior to the accident flight. On the day of the accident, the ATSB calculated that about 115 L of fuel remained on board, equivalent to about half tanks.
CCTV at Redcliffe airfield showed that prior to the flight, the wings of VH-WMM were not level while parked on the tarmac. The right wing at the tip was about 60 cm lower than the left, indicating a fuel imbalance, where the right wing contained a greater fuel quantity than the left wing. The right-wing low condition indicated that fuel crossflow from the left to right fuel tanks may have occurred while VH-WMM was hangered.
It is a known issue with the Rockwell International 114 that when the fuel selector is not placed in the OFF position when parked, fuel can flow from one tank to the other. Once a crossflow has started, the increasing fuel weight will also increase the lean of the aircraft, further promoting the fuel crossflow. This results in further uneven fuel distribution, and sometimes an overflow of fuel through the wing tank fuel vents when this imbalance fills one tank completely. The ‘local fix’ amongst the Rockwell 114 community to prevent the crossflow was to set the fuel selector to OFF when the aircraft was parked for an extended period of time. The possibility of fuel crossflow in VH-WMM was also known to the pilot.
A review of the aircraft’s logbooks showed that in April 2011, a maintenance intervention was performed on the fuel system due to a crossflow defect occurring when the fuel selector was set to BOTH fuel tanks. The fuel selector position of VH-WMM was unknown prior to the day of the accident, however it is likely that it was not selected to the OFF position.
Undercarriage system
The Rockwell 114 is equipped with a hydraulically operated undercarriage. The aircraft is fitted with an undercarriage warning system. A switch is mounted on the throttle quadrant which connects to an undercarriage warning bell, activating whenever the throttle is brought to idle while the undercarriage is retracted.
Stall warning
The Rockwell International 114 is fitted with an aural stall warning system, that provides an audible tone to indicate that the aircraft speed is slowing to a speed that it can no longer produce lift in flight.
On board video recorded the stall warning sounding 13 seconds after the engine experienced the large drop in power. The stall warning continued sounding intermittently throughout the remainder of the flight, indicating that the aircraft was only marginally maintaining airspeed above the stall speed. The stall warning horn activated multiple times during the final approach until impact with water. This indicates that the aircraft would have been within 3-4 kt of the straight and level flapless stall speed of about 63 kt.
VH-WMM was also fitted with a voice alert system. This unit was an electronic device which detected the activation of the existing aircraft stall and undercarriage warning systems. It was configured to place a voice warning directly into the pilot headset and through a built-in speaker in the unit itself. In this situation, a pilot who may not hear the aircraft-generated stall warning horns because of noise cancelling headsets, will have an electronic voice annunciation of the warning.
A witness who had flown with the pilot previously described the system as functional and that it was an effective warning tool. The passenger video detected one annunciation of ‘stall’ from the built-in speaker, just prior to impact. It is unknown if the system was alerting the pilot through the headsets during the flight, however it is likely that the system was functioning, as other pilots who had been on board for previous flights had observed its operation.
Engine information
The engine fitted to VH-WMM was last overhauled in July 1998 and had accrued about 988 flight hours in operation. The overhaul schedule as listed in Lycoming Service Instruction SI 1009BE was 12 years or 2,000 hours, whichever occurred first.
Although the engine had exceeded the calendar schedule of the manufacturer’s time between overhaul, this was permissible when the engine was maintained in accordance with the CASA on‑condition[8] requirements. At the last annual inspection in July 2021, the maintenance organisation had completed a piston engine condition report verifying the engine serviceability, which then permitted the engine to continue in service.
Site & wreckage information
Onsite examination
The wreckage was located about 1 km north of the Redcliffe airfield, on a tidal flat (Figure 3). The accident occurred about 40 minutes before high tide, and the water depth at the time of the accident was about 2 m. The aircraft impacted the water on a heading of about 218° in an upright, slight right-wing low, nose-down attitude, with the undercarriage in the extended position, and with the wing flaps retracted.
Ground scars observed on the tidal flat indicated that after entering the water, the aircraft nose wheel and propeller contacted the seabed leading to the aircraft overturning, resulting in sudden deacceleration and the aircraft coming to rest inverted. Witnesses described the water directly around the aircraft to be murky due to the mud and silt seabed having been disturbed by the aircraft impact. The left door (pilot door) was in a closed and latched condition when the ATSB arrived onsite. The right door was found by police divers to be slightly ajar, and difficult to open during the recovery operation.
Figure 3: VH-WMM accident site at low tide
Source: ATSB
The aircraft fuselage underside and right wing showed evidence of hydraulic[9] compression from impacting the water surface, and the engine had separated from the aircraft. The impact to the fuselage underside damaged the fuselage skins forward and aft of the wing main spar carry‑through, resulting in a large hole. The engine firewall had been punctured by the engine and the left rear side window was broken. The identified damage would have allowed water ingress into the fuselage. Fuel was visibly leaking from the right underwing fuel vent, and a strong fuel smell was evident at the site.
Wreckage examination
The wreckage was recovered to a secure storage facility for a detailed examination. ATSB investigators established flight control continuity before the rear of the fuselage and empennage were separated to facilitate transport from the recovery point.
A further flight control examination was performed with no defects noted. All components of the aircraft were identified and accounted for, and no pre-existing defects were noted with the airframe or engine.
Fuel system examination
Examination of the aircraft fuel system was carried out and found that the fuel selector was set to the LEFT tank at the time of the accident, and the auxiliary fuel pump was switched OFF. The gascolator was disassembled and contained water. After recovery of the wreckage, the fuel tanks’ contents were drained and consisted of:
right wing: about 85 L of AVGAS recovered, with no visible water
left wing: about 25 L of water, with no visible AVGAS.
Engine & propeller examination
The engine and propeller displayed no pre-existing damage. The propeller damage was indicative of low rotational energy at the time of impact and exhibited damage to the blades and spinner due to impact with the seabed. The engine was externally examined, all components were accounted for, and the engine was able to be rotated. The engine was disassembled and examined at a CASA-approved engine overhaul facility under the supervision of the ATSB. The engine showed no evidence of pre-impact mechanical discontinuity or defects which would inhibit normal operation.
Examination and testing of the engine fuel system was performed at a separate CASA-approved overhaul facility under ATSB supervision. Some system components had internal corrosion; however, this was most likely due to saltwater immersion. After removal of the corrosion, the system components tested correctly for operation.
The fuel control unit (FCU) initially could not be tested. A disassembly of the FCU found internal corrosion within the regulating system and the centre body seal was found to be separated. The centre body seal was examined at the ATSB’s technical facilities in Canberra. ATSB determined that the internal seal separation had occurred when the FCU was disassembled for examination and was not a prior defect.
Rockwell 114 procedures
Before take-off checklist
At each critical phase of aircraft operation, pilots refer to checklists to guide them through specific items to configure the aircraft for the next planned phase of the flight. The Rockwell 114 pilot’s operating handbook (POH)[10] stated in 3 separate checklists, ‘interior’, ‘before starting engine’, and ‘before take-off’ checklists, that the fuel selector valve is to be set to the BOTH position before the aircraft is ready for take-off.
Figure 4 shows the Rockwell 114 ‘before take-off’ checklist as detailed in the POH. Annotations highlight where the interruption occurred at the beginning of the accident flight, and the steps not completed as identified in the passenger video. The POH was located at the accident site at the rear of the pilot seatback, and passenger video showed that it was not accessed during the before take-off checks or during the flight.
Figure 4: Before take-off checklist
Source: Rockwell 114 pilot’s operating handbook, annotated by the ATSB
Third-party checklists
CCTV footage showed the pilot passing a folder to the adult passenger who placed it into the rear of the pilot seatback prior to engine start. This folder was found on-site in the rear of the pilot seatback pocket and contained the third-party checklists inside. Both of these checklists had interpretations of the Rockwell 114 POH checklists and had differences to the approved manufacturer’s documentation. This included changes in the checklist sequence, and omissions of some elements including the absence of one of the fuel selector checks.
CASA issued AC 91-22v2.0 Aircraft checklists, in November 2021 to provide guidance on establishing and using aircraft checklists and is derived from Civil Aviation Safety Regulation 91.095 Compliance with flight manual. This stated that any third-party checklists ‘must concisely convey each procedural step in correct sequence’ to ‘ensure aircraft are operated in a way that meets flight manual requirements and limitations.’
The US Federal Aviation Administration released a safety alert for operators (SAFO) 17006, in April 2017, warning pilots and operators of the risks of using commercially available and personally derived, third-party checklists.
An acquaintance who had regularly flown with the pilot reported that the pilot would also use generic mnemonic checklists that had been committed to memory, instead of the POH or the third‑party checklists. The commonly used mnemonic covered some, but not all of the checks required by the POH checklist.
Engine failure management
The Rockwell 114 POH emergency procedures checklist for an in-flight engine failure stated that the glide speed of 82 kt should be adopted, the auxiliary fuel pump selected on, mixture full rich, and the fuel selector be placed on the fuller tank to rectify possible fuel starvation.
Maintaining the published glide speed in flight gives the optimal amount of lift for the least amount of drag, thereby giving the greatest glide distance for the amount of height lost during the descent.
Rockwell 114 ditching procedure
A ditching is a controlled emergency landing on water. The Rockwell 114 POH ditching procedure identified that on approach to a ditching, the airspeed should be maintained at 82 kt.
The procedure followed on to list: transponder (if installed) set to 7700, and a mayday call should be made. The emergency locator transmitter should be activated if installed, seats, seatbelts, shoulder straps and loose objects should be secured, flaps should be up, cowl flaps closed, and the undercarriage retracted.
On final approach, flaps should be set to 20°, airspeed reduced to 74 kt, the undercarriage should remain retracted, and propeller set to high RPM. On touchdown, the elevator should be full aft, and the fuel selected to OFF.
Ditching guidance
In 2004 the ATSB made recommendation R20010258 which stated:
The Australian Transport Safety Bureau recommends that the Civil Aviation Safety Authority educate industry on procedures and techniques that may maximise the chances of survival of a ditching event. Part of that education program should include the development of formal guidance material of the type contained in the UK CAA General Aviation Safety Senses leaflet 21A Ditching.
In response to the recommendation CASA published CAAP 253-1(1) Ditching. This guidance was reissued in the form of AC 91-09 v1.0 and included but was not limited to the following safety advice about conducting a ditching:
For an aeroplane, it is likely to end up in a nose down vertical position after impact. Opening a forward door in these circumstances to escape may cause rapid water entry. Planning for this circumstance should include consideration of which exit might be opened prior to and after impact and briefing passengers on precautions when releasing seat belts. Any briefing should consider the prospect that the pilot may not be able to assist due to their prominent position where impact forces may be concentrated. An able-bodied passenger near an accessible exit would be the best resource for survivability in this situation.
The guidance also recommended unlatching a door prior to impact and providing passengers with a briefing, which included the brace position.[11]
Survival aspects
Passenger seating, exit location, and operation
The pilot (P) was seated in the front left seat location. The 3 passengers consisted of an adult and 2 children.[12] One child (C) was seated in the forward right seat next to the pilot and another child (C) was seated in the left-rear behind the pilot. The adult (A) passenger was seated in the rear‑right (Figure 5). Both aircraft doors were at the front row.
Figure 5: Seating positions
Source: Rockwell annotated by the ATSB
Figure 6 shows the aircraft doors, which were designed as both normal and emergency exits. Both doors had the same operation, which required 2 opening mechanisms to be manipulated, both when operating from inside or outside. One handle was located above the passenger/pilot head that needed to be rotated downwards to unlatch. The second handle was fitted to the forward lower part of the door and was a lever type arrangement, which was required to be pulled inwards to unlatch the 2 lower latches. Each door needed to be pushed outwards to open. There was no emergency jettison mechanism.
Figure 6: Location of door interior operating handles
Source: ATSB
CASA produced guidance for the allocation of passengers to exit row seats in multi-part advisory circular (AC) Passengers seated in emergency exit row seats for parts 121, 133 and 135 operators, however this AC was not applicable to private flights.
In addition to passenger suitability, the AC identified risks associated with seating inappropriate persons at exits and recommended that operational procedures should be used to address this risk.
Applicable risks included:
• exits being opened when they should not be e.g., a passenger opens the exit without assessing the outside conditions
• operation of exits by passengers who are not aware of the instructions specific to that exit e.g. how to open, remove and discard the exit
• passengers seated in an emergency exit row having an adverse reaction to the emergency due to inadequate briefings
• passengers that are not suitably able-bodied, lacking the strength and ability to remove the exit, attempting to open the exit, and delaying or impeding an evacuation process.
In addition, CASA guidance[13] identified that pilots should consider the possibility of incapacitation, and seat and brief an able-bodied person accordingly. However, passenger composition and operational considerations such as weight and balance must always be considered to determine passenger seat allocation.
(g) where the emergency exits are, and how to use them;
(p) the requirement that:
(i) passengers seated in emergency exit rows must be willing and able to operate the exit in the event of an emergency; and
(ii) such passengers must not have a condition that will cause them to obstruct the exit or hinder an emergency evacuation
While they had to be briefed, there was no legislative requirement to assess the suitability of a person[15] in an exit row for a private flight.
Guidance[16] on passenger safety briefings relevant for small aircraft operators included:
to include the brace position in the pre-flight safety briefing
to advise passengers to adopt the brace position in an emergency
if the flight involves overwater operations, passengers are briefed on ditching procedures.
Briefings in practice
A witness who the accident pilot regularly flew with reported that the pilot would normally provide a briefing about the seatbelts and the operation of the aircraft exits. The instructor who assessed the pilot in their most recent flight review provided confirmation of consistent elements normally included in the pilot’s briefing.
The ATSB was unable to determine what information was provided to the passengers prior to flight on the day of the accident. Video footage captured during the emergency showed that the pilot did not provide an in-flight emergency briefing to passengers about the nature of the emergency or what actions to take.
Occupant injuries
A post-mortem examination of the pilot and passengers was conducted on behalf of the Queensland Coroner. The examination found all occupants had sustained injuries which may have caused some incapacitation but were insufficient to have been fatal. The reports found that the deaths were consistent with drowning. The report also detailed evidence of injuries consistent with being caused by wearing a harness or seatbelt.
Other information
Pilot medical requirements
As outlined above, of the last 3 CASA aviation medical examinations, the pilot had not declared their diabetic status or diabetes medication to their CASA designated aviation medical examiner (DAME).
The disclosure to DAMEs was required due to the nature of type 2 non-insulin dependent diabetes and its effect on aviation participants. The CASA Clinical practice guidelines for type 2 diabetes website stated their concerns:
- Impaired autonomic function (hypoglycaemia awareness).
Pilots are permitted to hold a licence after a diabetes diagnosis. The CASA website further stated:
Type 2 diabetes is an aeromedically significant medical condition. Pilots and [air traffic] controllers who have been diagnosed with Type 2 Diabetes are required to ground themselves and notify this condition to their DAME.
In cases where the condition can be managed appropriately, and once cleared by the DAME, in accordance with the CASA guidelines, ongoing monitoring of the diabetes must be provided to CASA to prove that it is able to be managed and does not affect the pilot’s ability to fly.
Safety analysis
Introduction
Shortly after take-off, VH-WMM likely experienced fuel starvation leading to a complete loss of engine power. During the attempted return to the airfield without power, the pilot did not maintain an adequate glide speed, and the undercarriage was extended, thereby reducing glide range, which resulted in the aircraft colliding with water before it reached the airfield and becoming inverted about 170 m from shore.
This analysis will explore the power loss on take-off, flight planning and decision making of the pilot in command, and post impact survivability factors.
Checklist use
The passenger video identified that the pilot became distracted with a perceived engine problem during the before take-off checks and taxied back towards the groundcrew member. However, after realising that they had mis-identified the wrong engine control, the pilot then proceeded to the runway and conducted the take-off, without further completion of the required checks.
One essential aspect of the POH checklist stated that the fuel selector was to be set to BOTH. This ensures a positive supply of fuel can be delivered to the engine from both fuel tanks during take-off. There were two versions of the checklists on board the aircraft: the official aircraft POH included this item in 3 separate checklists, while the third-party checklists included it twice. While it is likely that the distraction affected the pilot’s completion of the ‘before take-off’ checklist items, the fuel selector was also not set to BOTH on the ‘interior’ or ‘before starting engine’ checks.
Should a third-party checklist be used, it must be checked to ensure that it contains the correct information that is applicable for the aircraft being operated and that the checklist is verified against the approved POH checklists. The ATSB was advised that the pilot sometimes referred to the third-party checklists, however it is unlikely that the third-party checklists were referred to on the day of the accident as the folder containing the checklists were located in the pilot seat back pocket and not readily at hand.
The POH was carried on board the aircraft on the day of the accident, and the passenger video showed it was not referred to during the flight.
On this basis, it is likely the pilot performed the before take-off checks from memory or used a mnemonic checklist to perform the before take-off checks which were ultimately interrupted. Before take-off, there is no time pressure (as there was inflight after the engine power loss), so there was opportunity to consult the written checklists to ensure all steps were completed. Conducting aircraft checks from items committed to memory can lead to checks being skipped or an assumption that a check has been completed when it has not. Also, when a checklist is interrupted, the habit of restarting from the beginning is a means of ensuring that all steps to be performed are done so in order and the checklist is complete.
Fuel imbalance
Analysis of CCTV imagery indicated it was likely that VH-WMM had a substantial quantity of fuel in the right wing, and that the pilot would have been aware of the imbalance after physically using a dipstick to check the aircraft fuel tanks during the pre-flight checks on the ground outside the hangar.
The fuel selector was found to be on the left tank after the accident and there was no video evidence of the pilot changing it during the flight. Therefore, the fuel selector was likely on the left tank during take-off. Due to the fuel imbalance, the left tank likely had minimal fuel to sustain engine operation during the climb out, which would result in the engine being starved of fuel, lose power, and begin to surge, and eventually stop. This is consistent with no fuel being found in the left tank after the accident.
If the fuel selector was placed on BOTH tanks, then it is likely, even with one fuel tank having most of the fuel and the other almost empty, that fuel supply to the engine would remain unaffected. Excess fuel in the right tank may have led to the observed fuel coming from the right wing during the flight.
Therefore, with the aircraft’s remaining fuel supply most likely in the right tank, and with the fuel selector likely set to LEFT prior to take-off, the engine became starved of the available fuel supply in the aircraft’s right fuel tank, leading to the engine stopping.
Engine power loss management
ATSB found that few, if any, initial emergency actions took place in response to the loss of engine power to rectify a possible fuel starvation as per the Rockwell 114 procedures. The aircraft had sufficient fuel for flight in the right wing, but the fuel selector was found to be selected to the now empty left tank, and the auxiliary fuel pump was off during the emergency.
In addition, the pilot did not maintain the published glide speed of 82 kt as demonstrated by the numerous stall warnings that sounded repeatedly, indicating a speed within 3-4 kt of the straight and level flapless stall speed (63 kt). Airspeed management was made more difficult by the extension of the landing gear, which may have been an automatic reaction by the pilot in response to hearing the undercarriage warning bell sound while the pilot was managing the emergency.
Not maintaining the glide speed and the landing gear extension increased the vertical rate of descent and reduced the glide range of the aircraft. However, video evidence suggests the pilot continued with their initial plan to glide to the runway. In addition, the extended landing gear was an unfavourable configuration for the subsequent collision with water.
There was no available evidence to indicate that the pilot’s response (actions and inactions) to the emergency was affected by a medical issue, or similar factors. However, the pilot was making decisions during the emergency under a high level of stress and time pressure. A substantial amount of research has shown that people often do not make optimal decisions in such situations.
Some commonly reported effects of stress and/or time pressure include attentional narrowing, with people searching fewer information sources (Staal 2004) and focusing on cues that are perceived to be the most salient or threatening (Burian and others 2005, Wickens and Hollands 2000). Working memory and the ability to perform complex calculations is impaired (Burian and others 2005), and the ability to retrieve declarative knowledge (or facts) from long term memory is affected (Dismukes and others 2015). In addition, a person under stress and time pressure will generally consider fewer alternatives, and not be as systematic when evaluating alternatives (Dismukes and others 2015, Staal 2004).
Collision with water
It is likely that the pilot never intended to ditch the aircraft. Rather, the reduced speed of the aircraft below the glide speed, exacerbated by the undercarriage extension, led to a reduced glide range and inability to reach the runway at Redcliffe. The sounding of the ‘stall’ alert just before the collision indicates the aircraft could no longer maintain lift and the aircraft collided with water 3 seconds later.
It is likely that under the stress of the situation, the pilot’s attention narrowed and their focus on landing back on the departure runway likely hampered their ability to consider a forced landing on water (ditching). Had the pilot recognised that the aircraft would not be able to glide to the runway, there was a brief opportunity (about 30 seconds) to attempt a controlled landing on water before the aircraft’s speed reduced to the stall speed.
If this had been the case, there were several actions the pilot would have had to remember (due to the limited time remaining) and complete to ensure a safe ditching. From the Rockwell 114 POH procedure, key actions were to ensure the undercarriage was retracted and the flaps were selected to 20° on the final approach to land on the water.
Use of flap in the final stages of the ditching would have provided a reduced stall speed, therefore allowing the aircraft to touch down at a lower, controlled speed. Touching down on the water while not at the appropriate speed, and with the undercarriage extended, contributed to the aircraft inverting after colliding the water.
Further, although there was no reference in the POH to the pre-impact position of emergency exits (cabin doors) prior to a ditching, unlatching of cabin doors can allow quick egress from the aircraft after ditching. In this accident, given the brief opportunity available for such considerations, it was not considered feasible that all actions were possible.
Due to the inverted orientation of the aircraft during the crash sequence and its submersion in murky water, the aircraft occupants were probably panicked, confused, and disorientated following the collision. Once the cabin filled with water, visibility would have been extremely low, which would have further reduced the likelihood of occupants being able to visually locate and operate the aircraft door handles. With the aircraft inverted, it is likely the occupants would have also been disoriented to the extent that it made opening the closed doors more difficult, reducing their ability to escape.
Pre-flight and emergency briefings
Research has shown that more knowledgeable passengers perform better in an emergency (Meng-Yuan, 2014). It could not be determined what information was provided to the passengers prior to flight, however based on accounts from persons who had flown with the pilot previously, including their flight instructor, it is likely that any briefing given did not include any information about the brace position or what to do in the event of a ditching. This meant that the passengers were likely unaware of actions that may assist survival such as opening the aircraft door or adopting a brace position.
Video footage recorded during the accident sequence showed that the pilot also did not provide passengers an in-flight emergency brief or instruct them on any actions they should take. This accident highlights the importance of providing instructions to passengers before a flight commences as often emergency situations are time limited and there may not be an opportunity to do so once something occurs.
Providing information on the adoption of the brace position or how to, and when to open an emergency exit in a ditching situation will increase the likelihood of passengers taking appropriate action in an emergency.
Passenger seating and emergency exit operation
Post-mortem examinations identified that the occupants of the aircraft were not fatally injured during the accident sequence. There was no readily available assistance nearby the accident site, and therefore the occupants would have had to extricate themselves from the aircraft.
The 2 emergency exits available to the occupants were more accessible to persons seated in the front of the aircraft. The exits required manipulation of both a handle on the door and a latch at the top. For the rear passengers, it is likely that they would have had difficulty (particularly with their seatbelt on) to reach the latch at the top of the door if required to operate the exit. The rear seat occupants would have also been restricted in accessing the doors and exiting the aircraft due to the presence of the front seat occupants.
After the accident, police divers were unable to open the pilot’s left door, and only opened the other (right) door with difficulty. For the injured pilot and right front seat occupant of VH-WMM, who was a child, it is highly unlikely they would have had the post-accident capability to open the doors. The right door was observed unlocked and ajar by police divers following the collision, suggesting the possibility that an attempt had been made to open the door.
Guidance suggests that pilots should determine the most appropriate person to assist in an emergency and to brief that person accordingly, therefore, in this case, seating a child who has less physical and mental capability rather than an adult next to an exit, meant that the most suitable person (the adult) was not in the best position to assist themselves and others in the event of an emergency.
Diabetes
The pilot had been diagnosed with type 2 non-insulin dependent diabetes which was managed with prescription medication by the pilot’s GP. A review of the pilot’s CASA aviation medical information indicated that this significant medical condition was disclosed in the pilot medical history as ‘unsure’ to the CASA DAME in the previous 3 aviation medical renewals, all of which were changed to ‘no' at the DAME examination prior to submission to CASA.
It was important to note that having type 2 non-insulin dependent diabetes did not mean that this condition would be an immediate disqualification of the pilot’s licence. However, due to the aeromedically significant nature of diabetes, it was important for this to be fully disclosed with the pilot’s DAME and to CASA. Without this interaction, it was a missed opportunity for the pilot’s condition to be monitored at a safe level required to exercise the privileges of a pilot’s licence.
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition, ‘other findings’ may be included to provide important information about topics other than safety factors.
These findings should not be read as apportioning blame or liability to any particular organisation or individual.
From the evidence available, the following findings are made with respect to the fuel starvation and collision with terrain involving a Rockwell International 114, VH-WMM, 1 km north of Redcliffe aircraft landing area, Queensland, on 19 December 2021.
Contributing factors
An unsafe condition was created by not referring to the approved checklists in the pilot operating handbook. Checklists located in the pilot operating handbook would have prompted the pilot on 3 occasions to set the fuel selector to BOTH prior to take-off.
A perceived engine problem distracted the pilot during the conduct of pre-take-off checks. After rectifying the issue, they did not complete the remaining pre-take-off checks (including fuel tank selection) before departure.
A fuel imbalance and likely an incorrect fuel tank selection prior to take-off, led to fuel starvation and engine stoppage soon after take-off.
The pilot, likely experiencing the effects of stress and time pressure following the engine power reduction and then stoppage, did not conduct initial emergency actions and attempted to return to the runway for landing but did not maintain glide speed, and the aircraft impacted shallow water prior to reaching the airfield.
During the return to the airfield, the pilot extended the undercarriage, contributing to the aircraft inverting when it collided with water. This likely resulted in occupant disorientation, difficulty in operating the exits, and reduced their ability to escape.
Other factors that increased risk
It is very likely that the passengers did not receive pre-flight information about the brace position or what to do in the event of a ditching. In the limited time available inflight after the power loss, the pilot also did not provide an emergency briefing or any instructions to passengers prior to impact with the water.
While the pilot was primarily responsible for the operation of the aircraft exits in an emergency, seating a child, who may require assistance, adjacent to an exit instead of an adult meant that a less suitable passenger was available to operate the exit if required.
The pilot had a diagnosed type 2 diabetic condition and did not directly declare this to the DAME during multiple medical renewals.
Sources and submissions
Sources of information
The sources of information during the investigation included:
Australian Government 2023, AC 91-09 Ditching v1.0, Civil Aviation Safety Authority, Canberra, ACT, viewed 25 January 2022, < AC 91-09 v1.0 - Ditching (casa.gov.au) >
Burian BK, Barshi I & Dismukes K 2005, The challenge of aviation emergency and abnormal situations, National Aeronautics and Space Administration Technical Memorandum NASA/TM-2005-213462.
Casner SM, Geven RW & Williams RT 2013, ‘The effectiveness of airline pilot training for abnormal events’, Human Factors: The Journal of the Human Factors and Ergonomics Society, vol. 55, pp.477-485.
Chaiken, S. R., Kyllonen, P. C., & Tirre, W. C. (2000). Organization and components of psychomotor ability. Cognitive Psychology, 40(3), 198-226.
Dismukes RK, Goldsmith TE & Kochan JA 2015, Effects of acute stress on aircrew performance: Literature review and analysis of operational aspects, National Aeronautics and Space Administration Technical Memorandum NASA/TM-2015-218930.
Kahneman D 2011, Thinking, fast and slow, Allen Lane London.
Klein G 1998, Sources of power: How people make decisions, Massachusetts Institute of Technology.
Landman A, Groen EL, van Passen VV, Bronkhorst AW & Mulder M 2017, ‘The influence of surprise on upset recovery performance in airline pilots’, The International Journal of Aviation Psychology, vol. 27, pp.2–14.
Lycoming Engines 2021. Service Instruction No 1009BE Time Between Overhaul (TBO) Schedules, viewed 7 December 2021, Lycoming Engines <Service Instruction No. 1009 BE | Lycoming>.
Staal MA 2004, Stress, cognition, and human performance: A literature review and conceptual framework, National Aeronautics and Space Administration Technical Memorandum NASA/TM-2004-212824.
Wickens CD & Hollands JG 2000, Engineering psychology and human performance, 3rd edition, Prentice-Hall International Upper Saddle River, NJ.
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
the Civil Aviation Safety Authority
the National Transportation Safety Board
the pilot’s last flight review flight instructor
the pilot’s ground crew member
medical subject matter experts.
Any submissions from those parties was reviewed and, where considered appropriate, the text of the draft report was amended accordingly.
Appendix
Sequence of events
The sequence of events below lists the key activities and audio from the passenger recorded video. This recording was started at 0902 and 25 seconds. The time listed in the table below is added to this time stamp. The video began during the taxi back toward the ground crew after the perceived engine problem.
Table 1: Sequence of events from accident flight video
Time (m:ss) from recording start
Time (m:ss) after take-off commencement
Activity
Comment
1:50
Stop at holding point
Discussing location of other traffic
2:18
WMM enters and backtracks runway 07
3:00 – 3:21
Take-off
3:30
0:09
Undercarriage retracts
Motor heard during gear retraction
3:56
0:35
Left turn
Aircraft over water
4:05
0:44
Engine RPM decrease
Pilot reduces power after take-off
4:09
0:48
Flaps seen retracting
Captured on video
4:15
0:54
Left turn
WMM now about 90° to runway heading
4:32
1:11
Engine RPM fluctuating
Distinct rise and fall of engine RPM
4:35
1:14
Large drop in engine RPM
4:38
1:17
Passenger asks pilot about fuel coming out of right-wing fuel cap
4:38 & 4:42
1:17 & 1:21
Two left turns
WMM now on downwind leg to airfield
4:48 & 4:51
1:27 & 1:30
Stall warning sounds
4:52
1:31
Engine stops
Distinct ‘whomp’ sound from engine, usually heard when a piston engine stops
4:56
1:35
Undercarriage warning bell followed by stall warning
‘Click’ sound, followed by a wind noise. Gear extension most likely set here.
5:02
1:41
Pilot speaking
Radio call for return to runway
5:18, 5:20 & 5:24
1:57, 1:59, & 2:03
Stall warning sounds
5:25
2:04
WMM turns directly toward runway
5:26 to 5:40
2:05 to 2:19
Stall warning multiple sounds
5:40
2:19
Right wing drops
5:42
2:21
Right wing drops
Electronic voice calls “stall”
Aircraft stall warning remains on
Electronic voice is an alert from the Voice Alert System – heard only once
5:45
2:24
Aircraft impacts water
Source: ATSB based on passenger mobile phone recording
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.
[1]Visual flight rules (VFR): a set of regulations that permit a pilot to operate an aircraft only in weather conditions generally clear enough to allow the pilot to see where the aircraft is going.
[2]Runway number: the number represents the magnetic heading of the runway. In this case, 07 equates to 70°.
[3]Radio communications on the common traffic advisory frequency at Redcliffe Aerodrome were not recorded.
[4]Psychomotor skills refer to the co-ordination of perception and action and require either complex perceptual discrimination or a complex motoric response (Chaiken and others, 2000).
[5]Records showed that the pilot had been prescribed 4 antihypertensive medications and had regularly been dispensed these medications in the months before the accident. Only 1 of these medications was detected in the toxicology analysis, however the type of analysis conducted would not detect the other 3 medications.
[6]Wet wing – the wing structure forms an integral fuel tank instead of a bladder or metal fuel tank.
[7]Gascolator – a fuel filter fitted at the lowest point of the fuel system.
[8]On-condition: Performed only when the condition of an item demands, instead of at scheduled intervals.
[9]Hydraulic: in this context is the deformation of the aircraft skin around its structural members (such as ribs). This deformation occurs by the action of water on the aircraft skin during the accident sequence.
[10]While Rockwell uses the term pilot’s operating handbook, other manufacturers, and generic terms may include aircraft flight manual, flight manual, owner’s handbook, operating manual, or owner’s manual.
[11]Brace position – adopted for ditching or crash-landing; shoes removed, bent forward with arms protecting head.
[12]A child as defined by CASA is a person who has turned 2 but has not turned 13.
[13]Civil Aviation Advisory Publication (CAAP) 253-1(1) Ditching (2004) now AC Ditching (2021).
[14]The previous CAO 20.16.3 Air service operations - carriage of persons required that passengers be briefed to determine if they were willing and able if seated in emergency exits and CAO 20.11Emergency and life-saving equipment and passenger control in emergencies required briefing on the location of the emergency exits, but not how to use them and did not include the brace position.
[15] A suitable person has been defined in the CASA dictionary as someone that is reasonably fit, strong, and able to assist with the rapid evacuation of the aircraft in an emergency; and would not, because of a condition or disability, including an inability to understand oral instructions, hinder other passengers during an evacuation of the aircraft in an emergency or the aircraft’s crew in carrying out their duties in an emergency.
[16]CASA guidance publications Cabin safety bulletin 12 - General aviation passenger briefings (2018),Civil Aviation Advisory Publication (CAAP) 253-1(1) Ditching (2004) now AC Ditching (2021), and Multi-part AC Passenger Safety Information (2021).
Preliminary report
Report release date: 28/02/2022
This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003.
The occurrence
On 19 December 2021, at about 0908 Eastern Standard Time,[1] a Rockwell International 114, registered VH-WMM, departed Redcliffe Aerodrome, Queensland, for a private scenic flight under visual flight rules. On board were the pilot and 3 passengers. The weather conditions were fine, with light winds from the east.
A number of witnesses located at the aerodrome, on the water in pleasure craft, and in other aircraft, observed VH-WMM (Figure 1). Witnesses at the aerodrome stated that, after VH-WMM took off from runway 07,[2] the landing gear was retracted and, a short time later, the engine ran rough for a brief period before stopping completely.
Another pilot was on their final approach for runway 07 and observed VH-WMM airborne. As that pilot was making their landing, they heard the pilot of VH-WMM broadcast on the radio that they were returning to the aerodrome.[3]
According to witnesses, the pilot of VH-WMM made 2 left turns, which were consistent with manoeuvring the aircraft back toward the western end of runway 07. During the return to the aerodrome, the pilot extended the landing gear. Description of the flight from the witnesses was consistent with controlled flight during this period.
As the aircraft neared the mangrove tree line to the north of the aerodrome, it was observed to descend and ditch into the water, about 170 m from the shoreline. During the ditching, the aircraft flipped over, coming to rest inverted in about 2 m of water.
Witnesses at the aerodrome and on board nearby boats, contacted emergency services and the Australian Volunteer Coast Guard. After being notified by one of the witnesses, a nearby vessel made its way to the aircraft, arriving about 5 minutes after the accident. The vessel’s occupants stated there was low visibility in the water and the fuselage was resting inverted on the seabed. This led to difficulty for first responders identifying how to open the aircraft doors.
The pilot of another aircraft flying overhead observed VH-WMM ditch in the water and contacted air traffic control (ATC) to advise them of the accident. That pilot remained overhead the accident site while boats arrived at the scene, and relayed information to ATC. A Coast Guard vessel arrived onsite; however, the crew were also unable to gain access into the aircraft’s cabin.
Queensland Police Service divers arrived a number of hours later, confirming that the pilot and 3 passengers had been fatally injured. The aircraft was destroyed.
Figure 1: Redcliffe Aerodrome and VH-WMM approximate flight path and accident site
Source: Google Earth, annotated by the ATSB
Context
Pilot information
The pilot held a valid Private Pilot Licence (Aeroplane) with the last flight review in July 2021, and a Class 2 Aviation Medical Certificate, valid until February 2023. The pilot held single and multi‑engine aeroplane ratings and endorsements for manual propeller pitch control, retractable undercarriage and formation flying. At the time of the accident, the pilot had about 504 hours total aeronautical experience.
Aircraft information
General information
The Rockwell International 114 is a 4-seat, single-engine aeroplane with fully retractable landing gear. It is powered by a 6-cylinder Lycoming IO-540 fuel-injected engine, and is fitted with a 3-blade constant-speed propeller.
VH-WMM was manufactured in the United States in 1977 and was first registered in Australia in May 2013. The last periodic inspection was conducted on 7 July 2021. At the time of the accident, VH-WMM had accrued a total time in service of 3,431.4 hours and had flown about 11 hours since the last inspection.
The aircraft type has 2 doors for pilot and passenger access, one on each side at the front of the aircraft cabin (Figure 2).
Figure 2: VH-WMM
Source: Nathen Sieben, modified by the ATSB
Site and wreckage information
The wreckage was located about 1 km north of the Redcliffe Aerodrome, on a tidal flat (Figure 3). The accident occurred about 40 minutes before high tide, and the water depth at the time of the accident was about 2 m.
The aircraft had impacted the water in a slight nose-down and upright attitude with the landing gear in the extended position. After contacting the water, the aircraft flipped over in the direction of travel, resulting in the aircraft being inverted.
The impact had torn the engine from its mounts and there was structural damage to the fuselage underside and right wing. Fuel was leaking from the right underwing fuel vent, and a strong fuel smell was evident at the site. The flaps were in a retracted position at the time of the accident.
Figure 3: VH-WMM accident site at low tide
Source: ATSB
Wreckage examination
A marine salvage company recovered the aircraft the following morning on high tide and, after floating the wreckage to the Scarborough boat ramp, it was transported to a secure storage facility for a detailed examination (Figure 4). Removal of the rear fuselage and engine was carried out to necessitate transportation by road.
The examination revealed:
all components of the aircraft were accounted for at the accident site
no pre-impact defects were identified
a quantity of fuel was removed from the aircraft
the engine and propeller were able to be rotated.
Figure 4: VH-WMM recovered for examination
Source: ATSB
Further investigation
To date, the ATSB has:
recovered and examined the aircraft wreckage
conducted witness interviews
conducted a disassembly and examination of the engine
examined the maintenance history of the aircraft
examined security camera footage from the aerodrome.
The investigation is continuing and will include:
a disassembly of the propeller
testing of retained engine components
analysis of data recorded from onboard systems
a review of mobile phone footage.
Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
A final report will be released at the conclusion of the investigation.
Purpose of safety investigations
The objective of a safety investigation is to enhance transport safety. This is done through:
identifying safety issues and facilitating safety action to address those issues
providing information about occurrences and their associated safety factors to facilitate learning within the transport industry.
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action.
Terminology
An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue.
Publishing information
Released in accordance with section 25 of the Transport Safety Investigation Act 2003
Ownership of intellectual property rights in this publication
Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia.
Creative Commons licence
With the exception of the Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this publication is licensed under a Creative Commons Attribution 3.0 Australia licence.
Creative Commons Attribution 3.0 Australia Licence is a standard form licence agreement that allows you to copy, distribute, transmit and adapt this publication provided that you attribute the work.
The ATSB’s preference is that you attribute this publication (and any material sourced from it) using the following wording: Source: Australian Transport Safety Bureau
Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly.