

Final report
Report release date: 28/10/2026
Investigation summary
What happened
On 6 February 2026, a Cessna 210N, registered VH-RDH, departed Goolwa Airport, South Australia, with 3 persons on board for a private local area flight. The persons on board comprised a flight instructor in the front right seat, a commercial pilot licence holder in the front left seat, and a passenger who held a recreational pilot licence in the second row left seat. The purpose of the flight was for the pilot in the front left seat to accumulate Cessna 210 flying experience.
The aircraft followed the coast to the east at about 2,350 ft for about 5 minutes and then commenced a right turn through south to track west along the coast back towards the mouth of the Murray River. As the aircraft approached the mouth of the river, the altitude increased to 3,375 ft and the groundspeed reduced to 74 kt before the aircraft commenced a rapid descent. Witnesses described it as a steep spiral descent and recorded video of the final moments before the aircraft collided with the water in a left turn spin. The occupants were fatally injured and the aircraft destroyed.
What the ATSB found
The ATSB concluded that it was likely that the flight instructor conducted a spin entry for the purpose of the pilot in the left seat practicing the spin recovery actions, which was conducted in an aircraft that was not approved for intentional spins. After entering the spin, it was likely that the pilot in the left seat mishandled the recovery during the incipient spin phase and the instructor did not intervene in sufficient time to prevent the aircraft entering a fully developed spin and recover within the height available.
The ATSB found that the instructor had a history of spin activity violations from which they had successfully recovered during the incipient phase, which likely provided them with the confidence to progressively lower the entry height they were using. These spin violations were not reported to the aircraft operator or the Civil Aviation Safety Authority, and therefore no action was taken to stop these activities.
The ATSB also found that the instructor's post-mortem examination indicated that they were at a higher risk of a cardiovascular medical event than predicted by their aviation medical exam, but it could not be determined if it contributed to the accident.
Safety message
The Civil Aviation Safety Authority (2020) advisory circular on spin avoidance and stall recovery training included a list of the key messages that are critical for the safe conduct of stall and spin training for pilots, instructors, flying training organisations and examiners. The first key message on the list was:
A spin must not be induced in aircraft not certified or approved for intentional spinning
Furthermore, the investigation identified several key themes associated with a reluctance to report unsafe behaviour. They included interviewees feeling a lack of power or feeling a lack of duty to deal with the situation. Therefore, the design and promotion of reporting systems should consider what barriers may exist to reporting flight discipline events and address them where practicable.
The occurrence
On 6 February 2026, at about 1608 local time, a Cessna 210N, registered VH‑RDH, departed from Goolwa Airport, South Australia, with 3 persons on board for a private local area flight. The persons on board comprised a flight instructor in the front right seat, a commercial pilot licence holder in the front left seat and a passenger, who held a recreational pilot licence, in the second row left seat. The purpose of the flight was for the commercial pilot licence holder to accumulate Cessna 210 flying experience. This was conducted under the supervision of the aircraft operator’s check and training instructor for Cessna aircraft, who was the flight instructor on board the aircraft.
Air traffic control (ATC) radar detected the aircraft at 1609:45 and the ATC system started generating a track for the aircraft at 1609:50 at an uncorrected altitude1 of 1,100 ft and groundspeed of 93 kt.2 Calculated barometric altitude3 started at 1609:58 and recorded the aircraft at 1,275 ft and a groundspeed of 93 kt (Figure 1). Goolwa Airport CTAF4 recordings captured a runway 19 upwind departure call from the instructor, that they were climbing through 1,000 ft to 1,500 ft and tracking coastal to the east. The departure call was followed by an amendment that the aircraft was climbing to 2,500 ft for smoother flying conditions.
ATC radar tracked the aircraft as it followed the coast to the east past Hindmarsh Island (Figure 2) at about 2,350 ft for about 5 minutes at about 130 kt. The aircraft then commenced a right turn through south to track west along the coast back towards the mouth of the Murray River (Murray Mouth) at about 136 kt. As the aircraft approached Murray Mouth, the altitude increased and as the aircraft climbed above 3,000 ft, the tracking data shifted slightly south (at 1620:17). At 1620:52, the aircraft’s recorded altitude reached 3,375 ft and the speed had reduced to 74 kt while maintaining a westerly track.
At 1620:57 the aircraft was recorded at an uncorrected altitude of 2,700 ft, still on a westerly track, and the speed had reduced to 66 kt. The ATC system then ceased tracking the aircraft, but it was captured a final time on radar at 1621:05, at an uncorrected altitude of 1,200 ft.
Figure 1: Air traffic control generated track with data points annotated
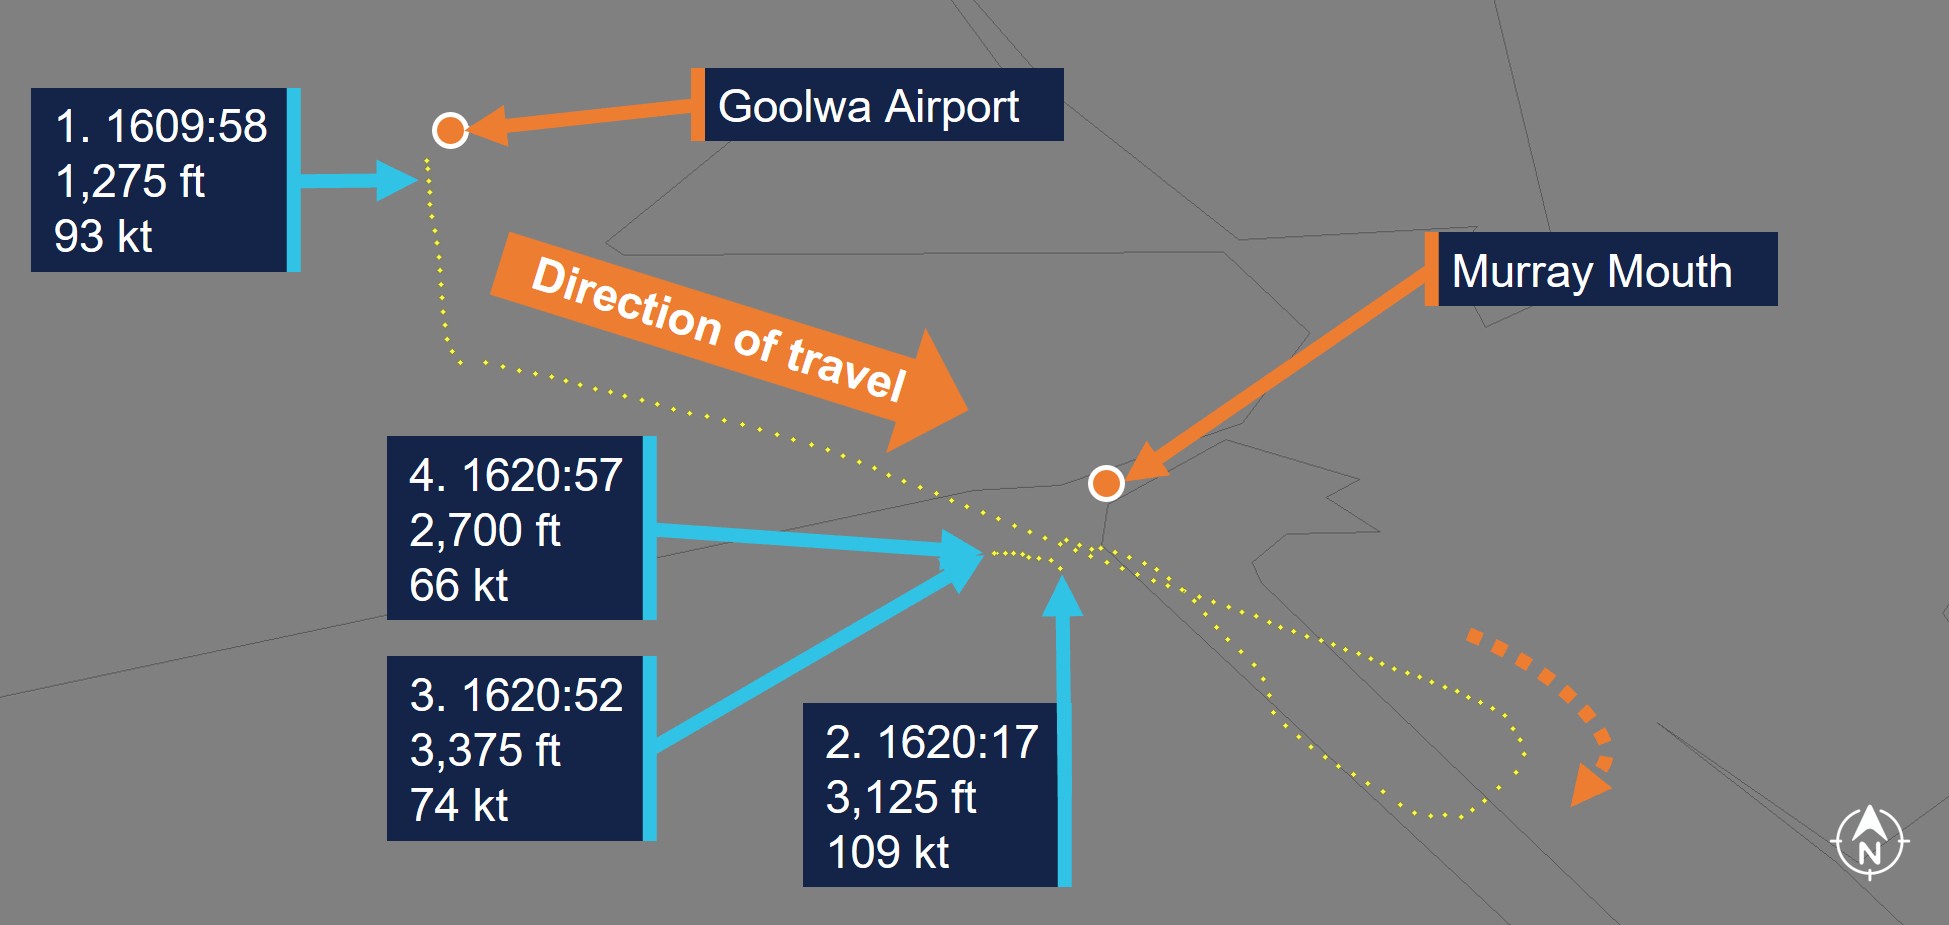
Figure 2: Accident flight path with key landmarks
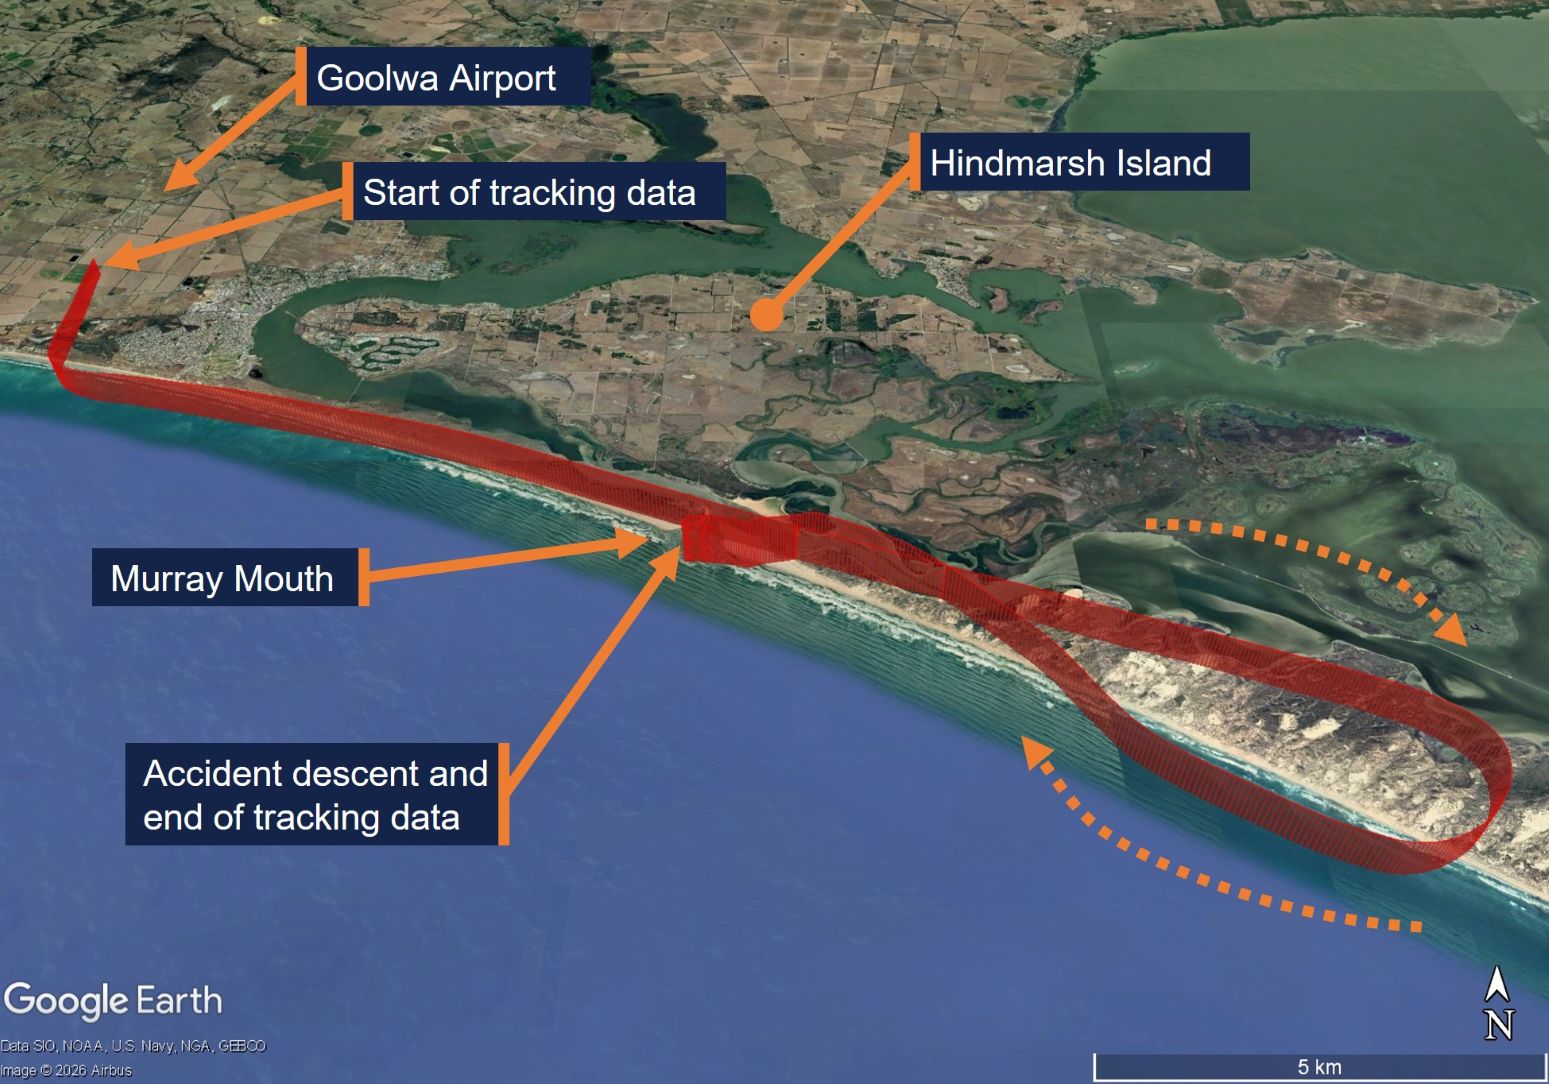
A witness located on the west side of Murray Mouth observed the aircraft in a steep spiral descent and, presuming the aircraft was a ‘stunt plane’, used their phone to record it. They subsequently captured the final moments of the descent and collision with water. The footage indicated that the aircraft was in a left turn spin just prior to colliding with the water in a steep nose down and left-wing low attitude, intact with the landing gear retracted.
The witness who recorded the video reported that the aircraft was rotating for the entire descent and several witnesses reported to the ATSB that the engine sounded like it was running until the collision. The witnesses also clarified that initial reports of a ‘bang’ from the aircraft was the sound of impact when it collided with the water. The 3 occupants were fatally injured and the aircraft was destroyed.
Context
Wreckage inspection
Onsite inspection
The wreckage was retrieved from the water by South Australia Police on the night of the accident, prior to the ATSB’s arrival at the site on the afternoon of 7 February 2026. The wreckage was heavily fragmented and missing the engine, propeller, wings, vertical fin and rudder. The main landing gear was found down and locked and the nose gear retracted. Several seat belts had been cut by emergency services personnel to remove the occupants.
The left front seat was attached to the seat rails in the forward position. However, the slide lock pins were bent backwards and out of the seat rails. It was fitted with an inertial reel strap to prevent abrupt inadvertent movement in flight. The strap was subsequently cut to remove the seat from the aircraft. The front right seat was within the wreckage but had separated from the seat rails. Damage to the rails indicated the seat was in the forward position when separation occurred. The seat lock pins were in the down (locked) position and appeared undamaged. The second row left seat was also within the wreckage and had separated from the floor of the aircraft with the seat legs bent sideways and fractured at the upper attachment weld. The second row right seat was not fitted. The rear seats (third row) were attached to the airframe.
The elevator control cables were identified, and the elevator trim surface was present and attached to the elevator. The elevator was free to move in the correct sense. Measurements of the elevator trim position were made, and an elevator control cable turnbuckle was removed and, in addition to the aircraft’s GPS unit, retained for further examination and analysis. The quality of fuel sampled at Goolwa Airport, where the aircraft was refuelled on the day of the accident, was found to be satisfactory.
Examination and analysis of the elevator
The elevator control cable turnbuckle had a bend in it indicating an applied force. The fractured wires had a predominant bend in the same direction as the applied force and had fractured at a point where there was a change in the material strength. There was corrosion-coloured contaminant around the wires, but after cleaning, no significant corrosion of the wires was observed. The majority of the wires were visible, and they exhibited fracture due to ductile overstress, which was concluded to be a consequence of the accident.
The elevator trim tab had a range of movement from 10° down to 20° up. The aircraft manufacturer reported that the elevator trim measurement taken onsite corresponded to about 10° of elevator trim tab up, which would produce a nose-down trim of the aircraft.
Examination of the GPS
The memory boards from the GPS were transferred to an undamaged, operational unit. However, when the unit was powered up it displayed the default initialisation latitude and longitude information (zeros) and no flight data could be retrieved.
While all of the occupants had electronic flight bag (EFB) apps, only one recorded a short section of the flight, which was on the outbound leg from Goolwa Airport and did not include the descent. Therefore, air traffic control data was used for analysis of the flight from departure to the top of descent, and eyewitness reports and video were used to assess the descent.
Analysis of the witness video
In the witness video, the aircraft was visible in 51 frames, which were extracted for analysis. The aircraft was rotating to the left in a steep nose down attitude of approximately 72° with the landing gear retracted and rotated about 218° while descending about 292 ft in 1.7 seconds. The rate of rotation was estimated as follows:
- 90° in the first 15 frames indicated 180°/sec
- 90° in the next 21 frames indicated 130°/sec
- 38° in the last 15 frames indicated 76°/sec.
There was no evidence of structural failure before the collision and individual control surface positions could not be distinguished due to pixelation at high zoom levels. However, the rate of rotation slowed significantly, which indicated that the aircraft was responding to control inputs and recovering from the spin.
Meteorological information
The Bureau of Meteorology automatic weather station on Hindmarsh Island recorded the wind from 180° at 15 kt and the QNH of 1017 hPa around the time of the accident. The witness reports and video imagery similarly indicated a southerly wind, together with clear skies.
Aircraft information
Introduction
The aircraft was a 6-seat Cessna Aircraft Company 210N,5 registered VH‑RDH (RDH), built in the United States (US) in 1981 and first registered in Australia on 28 April 1987. The aircraft was fitted with a Continental IO‑520L 6‑cylinder piston engine driving a 3‑blade constant speed propeller.
It was approved for VFR night operations in the operational category of charter and had accumulated 18,903.7 hours prior to the day of the accident. The weight of the aircraft on the accident flight was calculated to be about 1,492 kg, which was 232 kg below its gross weight limit, and the centre of gravity was in the mid‑range for its operating weight.
Maintenance
The aircraft was maintained under the Civil Aviation Safety Authority (CASA) Schedule 5, which required periodic inspections every 100 hours or 12 calendar months, whichever came first. The last 100‑hour inspection was on 11 December 2025, and the maintenance release was current at the time of the accident.
On the morning of the accident, the aircraft was used for pilot maintenance training under the supervision of a licenced aircraft maintenance engineer. It involved an oil and filter change, removal and re-installation of spark plugs, lock wiring and a tyre change. The flight controls were not disturbed, and the engineer checked all work done on the aircraft before flight and certified for the oil, oil filter and tyre change in the maintenance release.
Of note, on 13 September 2025, maintenance was conducted on the rudder and elevator, which included removal and refitting of the rudder. Both tasks included control travel and tension checks with the results satisfactory and correctly certified with independent inspections. On 15 September 2025, the aileron stops were checked for safety and certified with independent inspections.
The majority of airworthiness directives listed by CASA for the Textron Aviation (Cessna) 210 series aeroplane and Continental engine, model IO-520L, were cancelled or not applicable to the aircraft. Of those that were applicable, all were complied with except the following:
- exhaust manifold heat exchanger – inspection (16 (1))
- carry through spar lower cap – eddy current (2023-02-17).
However, there was no evidence that either contributed to the accident.
Certification and spin testing
The Cessna 210N aircraft is designated as a ‘Normal’ category airplane, as defined by Part 3 of the US Civil Air Regulations (CAR), effective 15 May 1956. CAR 3.20 “Airplane Categories”, paragraph (b), defines category N (Normal) as:
Airplanes in this category are intended for nonacrobatic, nonscheduled passenger, and nonscheduled cargo operation.
Within CAR 3.124 “Spinning”, paragraph (a) states:
Category N. All airplanes of 4,000 lbs. or less maximum weight shall recover from a one-turn spin… in not more than one additional turn… It shall not be possible to obtain uncontrollable spins by means of any possible use of the controls. Compliance with these requirements shall be demonstrated at any permissible combination of weight and center of gravity positions obtainable with all or any part of the designed useful load. All airplanes in category N, regardless of weight, shall be placarded against spins or demonstrated to be "characteristically incapable of spinning" in which case they shall be so designated.
The objective of the CAR 3.124 requirements was to assure that the aircraft would not become uncontrollable in the incipient phase of a spin. According to the manufacturer and CASA (2020), the practical purpose of this objective was to provide a margin of safety for recovery from a mishandled stall.
The manufacturer reported that the Cessna 210N either met or exceeded the requirements of CAR 3.124, and it provided a placard prohibiting intentional spins, which was required to be displayed in the cockpit ‘in full view of the pilot’. The cockpit placard prohibiting spins was not on the instrument panel of RDH, and the ATSB was unable to identify its location from the images available.6
In addition to the cockpit placard, the intentional spin prohibition was published in the limitations and emergency procedures sections of the pilot operating handbook (POH), which included the recovery procedure for an inadvertent spin. In regard to the use of the Cessna 210N for spinning, the manufacturer stated:
At no time did we ever intend to certify the 210N model as an aircraft approved for intentional spins. The Cessna 210 is a two hundred series airplane, a high-performance single engine that was meant for personal and business use, not as a trainer used for spins.
In comparison to the category N standard, aircraft certified for intentional spinning under CAR 3.124 were required to comply with the following:
(1) At any permissible combination of weight and center of gravity position obtainable with all or part of the design useful load, the airplane shall recover from a six-turn spin, or from any point in a six-turn spin, in not more than 1.5 additional turns after the application of the controls in the manner normally used for recovery.
Cessna 100-series spin characteristics
The manufacturer had produced several 100-series aircraft that were certified for intentional spinning. As a result of spinning flight accidents, it produced a guide on the spin characteristics of these models. In its guide, the phases of a spin were described as follows:
- entry
- incipient
- steady (fully developed)
- recovery.
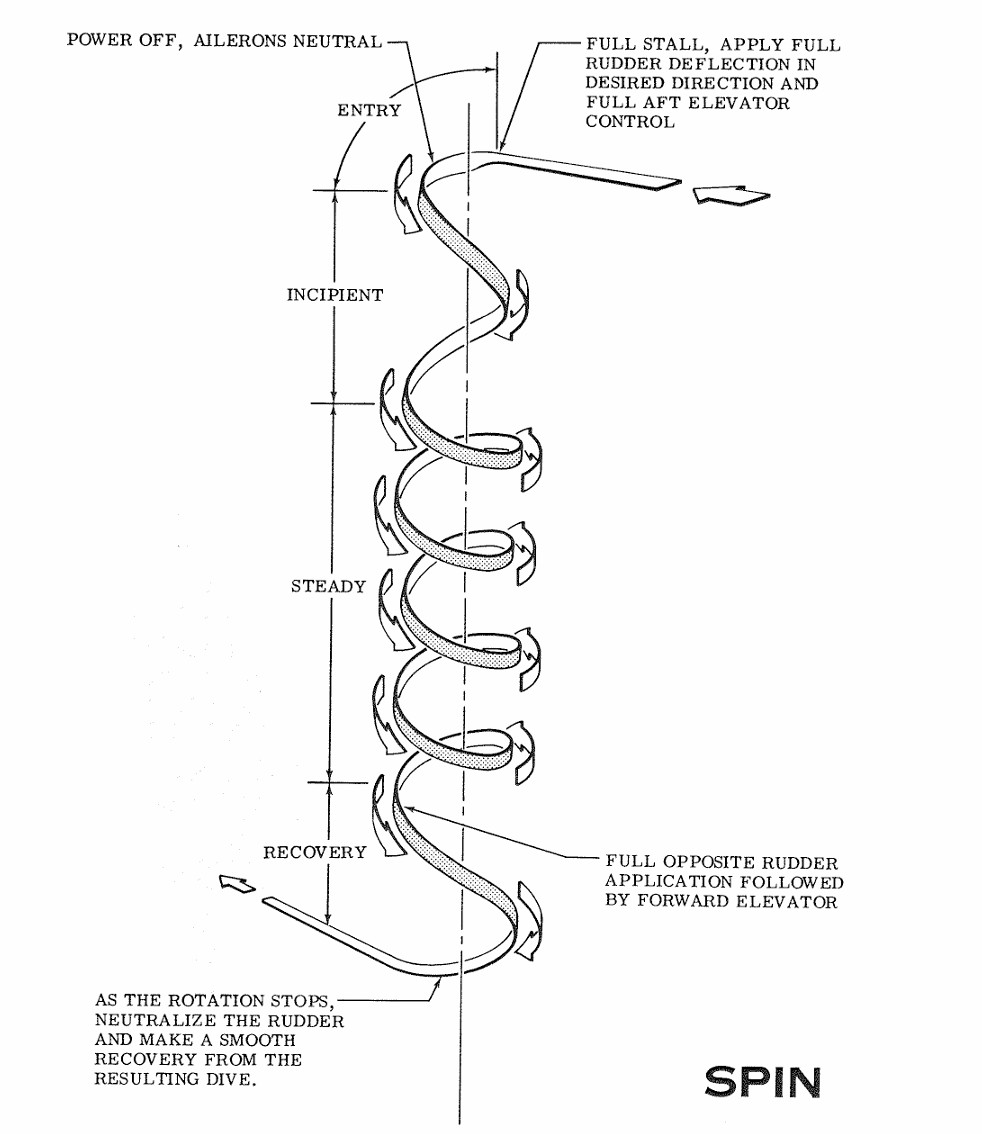
The entry phase is initiated when the aircraft is stalled in uncoordinated flight. The control inputs are depicted in Figure 3.
The incipient phase was described as follows:
The second or incipient phase covers that period of time from the spin entry to the fully stabilized spin. During this period the yaw being produced by a deflected rudder while the airplane is stalled is supplemented by the differences in lift and drag between the two wing panels. These parameters cause the rotating motion of the airplane to begin to increase.
In the fully developed phase:
Here, a more-or-less steady state spin results where the autorotational aerodynamic forces… are balanced by the centrifugal and gyroscopic forces on the airframe produced by the rotating motion… Because of the strong gyroscopic influences in the spin, improper aerodynamic control inputs can have an adverse effect on the spin motion.
For the purpose of this report, the recovery phase includes the introduction of anti-spin controls to cease the rotation and then recovery from the associated dive as per Figure 3.7
Figure 3: Phases of a spin
The manufacturer recommended spin entries be conducted at an altitude high enough to recover by 4,000 ft above terrain and that 1,000 ft of altitude loss should be allowed for a 1‑turn spin and recovery [incipient spin]. A 6‑turn spin [fully developed spin] would require more than twice the altitude loss of an incipient spin and the manufacturer recommended an entry height of 6,000 ft above terrain.
It stressed that the most important difference in the fully developed spin ‘is an increase in the length of recoveries … and to a lesser extent the amount of control input needed.’
The guide provided the following, further detailed, description of the potential adverse spin effects from improper control inputs:
Aileron variations from neutral can cause a different balance between the aerodynamic, inertia and gyroscopic forces and cause some delay in recoveries… even slight inadvertent aileron deflection in the direction of the spin will speed up rotation and delay recoveries… reversing the sequence of rudder-elevator inputs or even just slow, rather than brisk, inputs may lengthen recoveries… it is important, particularly in this steady spin phase, in addition to using the correct control application and proper sequence of control application, to HOLD THIS APPLICATION UNTIL THE RECOVERIES OCCUR. In extreme cases, this may require a full turn or more with full down elevator deflection.
Regulatory spin height limits
According to the CASA flight instructor’s manual (2007), spins should be taught from an altitude that will permit recovery by 3,000 ft above terrain, which is the minimum height limit for an initial spin endorsement. The CASA Part 61 Manual of Standards permitted the spin manoeuvre to be recovered by the pilot’s aerobatic height limit, or flight manual limit if one applied. Therefore, the minimum recovery height from a spin could be reduced below 3,000 ft if a pilot’s aerobatic height limit was lower and there were no flight manual limits to prohibit it.
Personnel information
Flight instructor
Qualifications and experience
The instructor held a Commercial Pilot Licence (Aeroplane) with a single-engine class rating and the endorsements required for the Cessna 210N aircraft. Their flight instructor rating was endorsed for ‘Grade 2’ (aeroplane), ‘Spinning’ and ‘Aerobatics’ training. On 27 November 2025 their aerobatics height limit endorsement was lowered from 3,000 ft to 1,500 ft.
They held a valid Class 1 aviation medical certificate with a reading correction restriction when exercising the privileges of their licence. The instructor recorded 8,692 hours flying experience on their last medical application on 24 October 2025. The ATSB was unable to establish the instructor’s total flying experience in the Cessna 210, but the maintenance release for VH‑RDH indicated the instructor had accumulated 39.5 hours in the previous 2 months.
Previous employment
The instructor started work as a flight instructor in the Recreational Aviation Australia (RAAus) system with an operator at Aldinga Airport, South Australia. The operator provided flight training under the RAAus and CASA flight training systems, and the instructor subsequently gained their CASA flight instructor rating and was employed casually to deliver training under both systems and to work as a charter pilot. The instructor was assessed competent to conduct spin and aerobatics flight in September 2006 and to deliver spin and aerobatics training in April 2009.
The instructor was involved in 2 incidents reported to RAAus while working for the operator at Aldinga. The incidents were classified as a runway excursion (2018) and near collision (2022). The instructor’s employment with the operator at Aldinga concluded on 29 April 2024.
The operator at Aldinga reported it had a history of student complaints with the instructor. As a flying school, it advocated stall and spin training provided it was suitable for the pilot and aircraft. However, the operator reported that the instructor did not always respect the boundaries of what the operator considered appropriate flying. The operator reported that the instructor was a ‘good handling pilot’ and good with clients in the charter role but felt that it received more student complaints about the instructor than about the rest of its staff combined. An example of inappropriate flying described by the operator was the instructor performing steep turns and wingovers8 during trial instructional flights.
Whenever the head of operations (HOO) received a report of what they considered inappropriate flying, they debriefed the instructor. The HOO reported that the instructor was always receptive to the debriefings and believed that it was enough to moderate the instructor’s flying behaviour. However, after a period of time there would be a recurrence. They also received a report of inappropriate flying by the instructor after the instructor had left their employment.
The HOO reported that after the instructor left their employment, there was an unplanned formation flight by the instructor in RDH with one of their own staff members in another aircraft with a student on board. This occurred in January 2026, and video footage of the event was obtained by the ATSB (Figure 4). There were 4 persons on board RDH, which included the accident pilot as one of the passengers.
Figure 4: Unplanned formation flying

Employment at Goolwa
About 3 years prior to the accident, the instructor introduced themselves to the head of training and checking (HOTC)9 of an operator based at Goolwa Airport. The introduction occurred at Aldinga Airport, where the HOTC was conducting charter flights for a health services provider. As the charter work became busier, the HOTC offered the instructor some casual charter pilot work. The instructor subsequently joined the operator’s business as a casual employee in September 2023, while continuing to work casually for the Aldinga operator.
The Goolwa operator also conducted RAAus flying training and this part of its business was affiliated with a separate operator at Aldinga, which was a business competitor to the instructor’s employer at Aldinga. Therefore, the HOTC did not consider it appropriate to approach the instructor’s current employer at the time for a reference. Instead, the HOTC talked to other industry contacts and received positive feedback about the instructor. The health services client also knew the instructor from a previous contract and wanted them to join the contract with the Goolwa operator.
In July 2025, the Goolwa operator added Marree in central South Australia as a temporary base to its operations manual. A Marree business owner had purchased 2 Cessna 210 aircraft, which included RDH, and contracted the Goolwa operator to provide Lake Eyre scenic flights from Marree. The instructor collected the aircraft from Darwin, and, in September 2025, the Goolwa operator became the registered operator of RDH. Additionally, its operations manual was amended to delegate the training and checking role for its Cessna aircraft to the instructor.
As the 2025–2026 summer period approached, the aircraft owner and operator decided to move RDH from Marree to Goolwa and offer a package deal of 10 hours Cessna 210‑flying experience and a day of pilot maintenance training, which was advertised on social media. The operator managed the bookings and delegated the responsibility for supervising the flying activities to the instructor. This provided ongoing work for the instructor10 and avoided the requirement to add any pilots to the aircraft insurance.
On 4 February 2026, the instructor received their Part 141 flight training approval certificate from CASA. The instructor’s Part 141 operations manual, dated November 2025, included training for spin endorsement and stated:
Spin training may be conducted by an appropriately qualified instructor in an appropriate aircraft, to familiarise students with the characteristics of a spin and to introduce them to the basic spin recovery technique.
Pilot
Qualifications and experience
The pilot held a Commercial Pilot Licence (Aeroplane) with a single‑engine class rating and the endorsements required for the Cessna 210N aircraft. Their licence was issued on 22 August 2025, and they had accumulated 199 hours flying experience, which included 190.4 hours on the Diamond Aircraft Industries DA40 and DA42 aircraft, and 8.6 hours on the Cessna 210 in RDH.
The Diamond aircraft are non-aerobatic and therefore no spinning or aerobatics was conducted on their commercial pilot licence course. They held a valid Class 1 aviation medical certificate with no restrictions.
The pilot’s flying hours in RDH comprised 2 flights logged as pilot in command under supervision with the instructor recorded as pilot in command (PIC), and 5 flights logged as PIC with the instructor recorded as ‘Other pilot or crew’.11
The pilot attended the pilot maintenance training at Goolwa Airport on 6 February 2026 and in the afternoon, they boarded the aircraft as a passenger seated in row 2 for a session of circuits12 before moving forward to the front left seat for the accident flight, which was to be their last flight in their 10‑hour package. The pilot flying the circuits disembarked the aircraft after they completed their circuit training flight.
Pilot’s attitude to spins
The ATSB interviewed the pilot’s family and several other pilots conducting the Cessna 210-flying experience at Goolwa. The Cessna 210 pilots had trained at Parafield Airport and, in some cases, had graduated from the same flying school as the accident pilot. They were of a similar age, and some were already acquainted with each other before starting their flying at Goolwa in RDH. It was also a common practice for them to fly as a passenger in the aircraft to maximise their experience. Consequently, they had frequent social interactions with each other throughout the summer before and after flying as well as during pilot maintenance training.
The accident pilot spoke highly of the instructor to their parents and was scheduled to travel to Darwin, Northern Territory, the following week to pursue commercial pilot work opportunities. The pilot’s parents provided copies of videos the pilot had taken with their phone while on board RDH as a passenger, which included the instructor demonstrating a steep turn, stall and wingover. In addition, there were several videos taken from the ground of an aerobatics practice flight at Goolwa Airport, which included expressions of excitement from the pilot when they filmed the aircraft perform a spin.
The Cessna 210 pilots who spoke with the pilot about the spinning activities described the pilot as someone who enjoyed it and provided the following comments:
• [Pilot] would certainly want to repeat it… I am unsure of whether [pilot] knew it was against the POH for the 210… In the same way that I did, [pilot] would have trusted [instructor’s] judgement on the ability to conduct a spin13 (see the section titled Spin violation incidents)
• [Pilot] enjoyed recovering [from spin] because [pilot] wasn’t exposed to that at [flying training school] … [pilot] did want to do it… [pilot] did ask me if I wanted to spin… was very into aerobatics
• [Pilot] always go on about spins… I can tell you [pilot] definitely wanted to do one
• [Pilot] did mention it [spinning] a couple of times… [pilot] said, “I’d really love to do spinning.”
During the maintenance activity on the day of the accident the pilot mentioned their plans for their last flight in RDH with 2 witnesses14 in attendance. The pilot reported to one witness that they planned to fly to Strathalbyn, conduct circuits and return to Murray Mouth for airwork.
The pilot mentioned spins to another witness, who reported that the pilot seemed keen to conduct the manoeuvre. However, the pilot had mentioned to this witness that the instructor would only do it with a maximum of 3 persons on board. Consequently, when the witness saw 4 persons board the aircraft for circuits after the pilot maintenance training was completed, they assumed the pilot would not conduct spinning on their last flight.
Passenger
The passenger held a Recreational Pilot Licence (Aeroplane) with a single‑engine class rating, issued on 18 December 2025. Their licence restricted them to aeroplanes with a maximum take-off weight of 1,500 kg and therefore they could only fly the Cessna 210N with an instructor.15
They attended the pilot maintenance training on 6 February 2026 and were scheduled to fly the aircraft with the instructor the following morning. However, there was a spare seat available on the aircraft after the pilot maintenance training ended and consequently, they boarded the aircraft for the circuit session in the rear seat and then moved forward to the row 2 left seat for the accident flight.
Medical and pathological information
Introduction
The flight instructor was ejected from the aircraft in the collision, and the pilot and passenger were found in their respective seats. A pathologist attended the accident scene and conducted an initial assessment of the 3 occupants before they were transported to Forensic Science SA for toxicological testing and autopsy.
The ATSB obtained copies of the toxicology and autopsy reports for the flight instructor and the pilot. The extent of the recorded trauma injuries indicated the accident was not survivable. Therefore, survivability is not discussed in this report.
Flight instructor
Toxicology analysis for the instructor found 2% carboxyhaemoglobin and 3 mg/L paracetamol present. There was no alcohol or other drugs detected.16 The pathologist concluded that toxicology findings were not relevant to the death and that it occurred rapidly due to the combination of severe injuries, consistent with a light aircraft crash. However, the pathologist also found evidence of ‘severe coronary artery narrowing’ (coronary artery disease) that ‘could potentially induce an acute medical event leading to incapacitation, but this cannot be confirmed or excluded pathologically.’
The CASA aviation medicine section was aware that the instructor had health conditions that required monitoring. The instructor’s cardiovascular disease (CVD) risk score was initially calculated to be 3%,17 which was deemed low risk, but they were referred to a cardiologist based on their high cholesterol levels. While the instructor had elevated low‑density lipoprotein (LDL)18 cholesterol, this was not a variable in the CVD risk calculator.
The cardiologist noted that the instructor had multiple cardiovascular risk factors, and they discussed lifestyle modification. The cardiologist reported that the instructor’s blood pressure was ‘on target’ and they were ‘in sinus rhythm as confirmed on resting ECG [electrocardiogram] with heart rate 65.’ They prescribed 10 mg of the medication Rosuvastatin daily and considered it likely that in the future the dosage would need to escalate, and Ezetimibe would also need to be prescribed, to achieve the lower target value of LDL cholesterol.
The ATSB consulted with CASA about the instructor’s medical exam results and autopsy findings. CASA confirmed the instructor was going to be re‑issued with their Class 1 medical certificate19 but agreed with the pathologist’s conclusion that an acute medical event could not be confirmed or excluded pathologically. Furthermore, CASA considered the pathologist’s findings indicated that the instructor was a higher cardiovascular risk than predicted by the CVD calculator.20
Pilot
The pathologist noted at the site that the pilot had their seatbelt strap in the closed/locked buckle position, but no definite shoulder harness was identified. Toxicology analysis for the pilot found 2% carboxyhaemoglobin present but no alcohol or other drugs were detected. The pathologist found no ‘overt’ evidence of natural disease or toxicology contributed to death, which was from the trauma associated with a light aircraft crash.
Flight instruction
According to the United Kingdom Civil Aviation Authority, flight instruction ‘means imparting of aeronautical knowledge through a combination of ground schooling, simulated, and practical flight instruction.’21 The CASA flight instructor manual (aeroplane) (2007) description of how flight instruction should be delivered included the following points:
It is imperative that the student receives an adequate briefing prior to attempting to learn a lesson in the air. The pre-flight briefing is aimed at confirming recency to theory taught in theory lessons or self-study… Airborne sequences must follow an acceptable method of teaching like: Demonstrate, Direct then Monitor… Generally the instructor should first demonstrate all air exercises and then the student should try them. Some exercises, for example spinning, are best taught by first demonstrating, then having the student manipulate the controls together with the instructor and then trying it with the instructor monitoring.
A ‘demonstrate’ is conducted by the instructor with the student observing and not handling the controls. If the instructor wishes the student to feel the size, rate or sequence of their control inputs during a demonstrate, then they should preface the demonstrate with a phrase, such as ‘follow-me-through and note…’ The instructor should then question the student afterwards to confirm they understood the teaching point. ‘Direct’ involves the instructor talking the student through the control inputs while the student is manipulating the controls. ‘Monitor’ involves the instructor observing the student only.
An instructor might follow-through on the controls while the student is flying if they assess that a rapid intervention may be needed to avoid an accident, such as during spin training (CASA, 2007). However, there is an associated risk that a student might over‑control in response to sensing another force on the controls. In an extreme case this could result in the instructor and student applying opposing control inputs if the instructor does not clearly announce taking over control. Hence, handover and takeover drills should be briefed and used to prevent confusion on who is manipulating the controls (CASA, 2007).
The ATSB interviewed a pilot who converted from their RAAus pilot certificate to a CASA recreational pilot licence with the accident instructor on the Cessna 172R aircraft, an aircraft approved for intentional spins in the utility category. There was no spin requirement for the conversion, but the pilot asked the instructor if they could be shown a spin recovery and the instructor then conducted 3 spins with them. The first spin was a demonstrate and on the second spin the pilot followed through on the controls. On the third spin the instructor allowed the pilot to manipulate the controls during the recovery under their direction; ‘I would say it was basically half [instructor] half me in the recovery.’ The pilot reported that on each occasion it was ‘recovery after 1 rotation’.
In 2020, CASA released version 1.0 of its advisory circular (AC) on spin avoidance and stall recovery training (AC 61-16 v1.0). The AC highlighted the need for instructors to observe the published aircraft limits as follows:
Understanding of aircraft limitations at all times is essential, especially when conducting advanced stall with wing drop training, and training in recovery from a spin at the incipient phase. In particular, spinning must not be actively induced in aircraft not certified for intentional spinning with the intention of teaching recovery from ‘incipient spin’.
Spin violation incidents
Introduction
Shortly after the accident, the ATSB witness mailbox received reports that the accident flight instructor had previously conducted spins in RDH and in an RAAus aircraft. In response, the ATSB interviewed the following individuals regarding the allegations:
- operators from Parafield, Aldinga and Goolwa
- CASA representatives
- pilots employed by the Goolwa operator of RDH
- pilots who submitted reports to the ATSB witness mailbox
- pilots who participated in the Cessna 210-flying experience package offered by the Goolwa operator.
The interviews revealed 7 separate flights with a spin violation activity instigated by the instructor prior to the accident flight, and the ATSB was able to retrieve recorded data of the spin manoeuvres in 4 of those flights, which captured 6 spins. The recorded data was in the form of onboard video, Airservices Australia WebTrak data and/or electronic flight bag (EFB) data.
November 2023
The earliest reported instance occurred on 5 November 2023 when the instructor was providing transition training on a Cessna 182Q for one of the Goolwa operator’s charter pilots at Aldinga Airport. The purpose of the training was to prepare the pilot to use the aircraft as a backup for the health services charter contract out of Aldinga and the flight was recorded with EFB 1‑second data points. The Cessna 182Q was not approved for intentional spinning.
During the flight, the instructor briefed the PARE acronym (Power – idle; Ailerons – neutral; Rudder – opposite spin direction; Elevator – forward to unstall the wings) and then demonstrated a spin, which the EFB recorded as occurring between 4,659 ft and 3,813 ft (846 ft altitude loss). The pilot did not follow-through on the controls and assumed the spin was a permitted manoeuvre because the instructor conducted it. They reported that they would have debriefed the flight with the Goolwa operator HOTC but did not believe the debrief would have included the specific manoeuvres.
February 2024
On 24 February 2024, the instructor conducted an RAAus flight review of a pilot, who also held a CASA flight instructor rating, in an RAAus-registered aircraft at Aldinga Airport. The instructor briefed the pilot that they wanted to see stalls, spins and spiral dives for the review. When the pilot responded that RAAus aircraft could not be used for spinning, the instructor replied that the aircraft was certified for spinning and therefore they would do it.22
During the flight, the instructor demonstrated how they taught spinning and then directed the pilot to conduct at least 2 incipient spins. The pilot subsequently became nauseous from the upset recovery exercises, which included multiple stalls, spins and spiral dives, and did not complete any circuits on return to the airport. Consequently, the instructor did not certify the flight review as completed.
As the flight had been booked through the instructor’s Aldinga employer, the Aldinga operator HOO later contacted the pilot about the incomplete flight review and learned what had occurred. They apologised to the pilot for how the flight review was conducted and debriefed the instructor to the effect that it had not been conducted appropriately. The pilot and HOO reported to the ATSB that as the aircraft was certified for spins, and both pilots were endorsed to conduct spins, they didn’t consider it to be a safety concern at the time and therefore did not warrant reporting.
July 2025
A pilot who was employed by the Goolwa operator in 2025 received line training from the instructor in a Cessna 172R with another of the operator’s pilots. At the end of their training on 19 July 2025, with the pilot seated in the rear right seat behind the instructor and the other pilot seated in the front left seat, the instructor asked them if they wanted to see what a spin looks like and talk them through the recovery, which they subsequently did. Intentional spins are only permitted for the Cessna 172R in the utility category23 and the POH limitations section stated:
In the utility category, the rear seat must not be occupied and the baggage compartment must be empty.
A rear seat passenger will shift the centre-of-gravity aft, and the manufacturer provided the following warning in their spin characteristics guide:
…extremely aft c.g. locations will tend to promote lengthened recoveries since a more complete stall can be achieved. Changes in airplane gross weight as well as its distribution can have an affect on spin behavior since increases in gross weight will increase inertia.
Neither of the pilots challenged the instructor about spinning the aircraft with a passenger in the rear seat and it wasn’t until after the RDH accident that they realised the spinning shouldn’t have been performed.
Cessna 210-flying experience pilots
Pilot 1
The ATSB received reports of spin activities in RDH that started in December 2025. The first was a pilot who graduated from their commercial pilot training program in mid‑2025 and conducted the 10‑hour Cessna 210 package in mid‑December. The instructor delivered upset recovery training to the pilot on their second day flying the aircraft, which the pilot described as stalls, spiral dives and a spin recovery demonstration.
The instructor briefed the PARE acronym to the pilot inflight and conducted a 2‑turn spin, which started from about 4,500 ft, in the same area as the accident flight. The pilot followed through on the controls to feel the instructor’s recovery actions.
Pilot 2
Pilot 2 graduated from the same commercial pilot training program as pilot 1 in mid‑2025 and started their 10‑hour package in RDH a couple of days after pilot 1. Pilot 2 conducted their first flight in the aircraft, which included stalls, spiral dives and a spin, on 13 December 2025 with pilot 1 seated in the rear.24. The stalls and spiral dives were conducted as demonstrate and monitor by the instructor. The instructor asked pilot 2 if they had seen a spin (which they hadn’t) and stated that every pilot should be shown a spin recovery at least once in their training.
Pilot 2 reported that they did not know at the time that intentional spins were prohibited in the aircraft but did query if they should be doing it in a Cessna 210, to which the instructor responded that they ‘had approval’. Pilot 2 did not enquire any further about the ‘approval’ but did also query if they should be doing it with a passenger in the rear, to which the instructor replied that it was fine.25
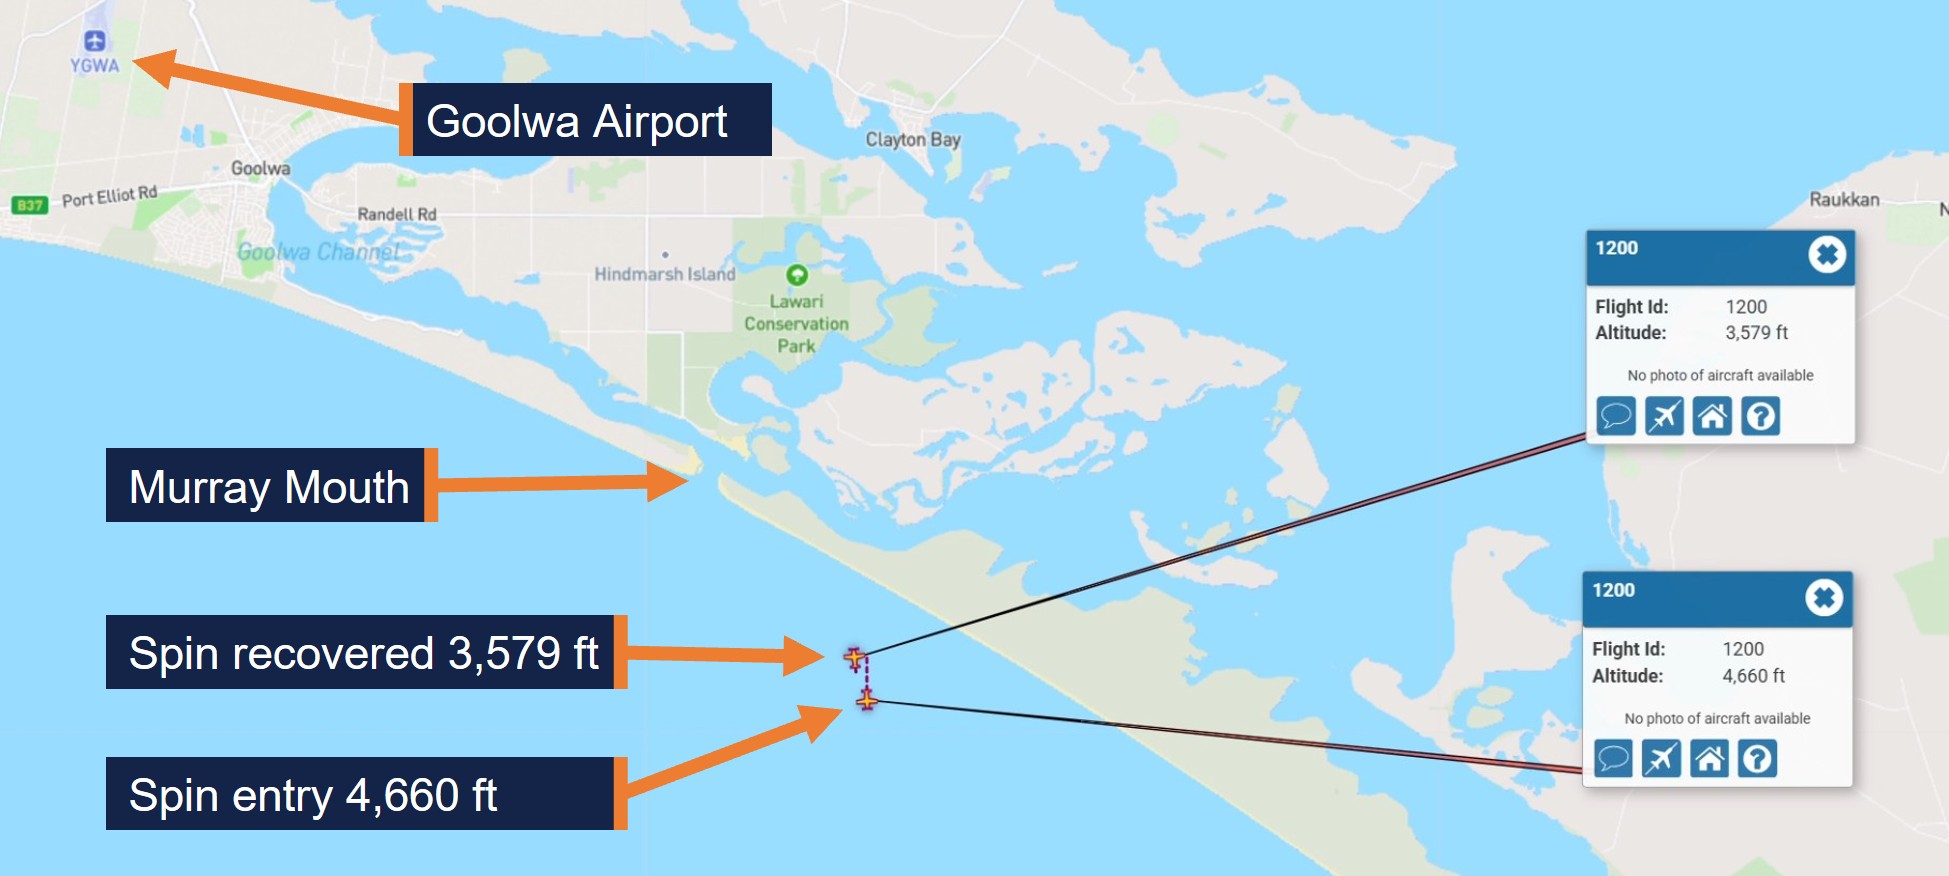
Pilot 2 followed through on the controls to feel the aileron and rudder inputs for a 1‑turn spin followed by the recovery. WebTrak data recorded the spin occurred between 4,660 ft and 3,579 ft (1,081 ft altitude loss) (Figure 5). The spin was also recorded on video from the rear seat by pilot 1, which was obtained by the ATSB.
Figure 5: Spin demonstration in VH-RDH on 13 December 2025
Pilot 3
Pilot 3 started flying RDH with the instructor at Goolwa in December 2025 while working at a flying school at Parafield. They had previously graduated as a commercial pilot from a different flying school to the other pilots attending Goolwa. On 7 January 2026, the accident pilot arrived at Goolwa for their first flight in RDH and initially boarded the aircraft as a passenger for a circuit training flight with pilot 3 as the pilot flying. Pilot 3 then moved into the row 2 left seat for the accident pilot’s first front left seat flight in the aircraft. The instructor had conducted general handling exercises and circuits with pilot 3, but no spins.
After the airwork started, the instructor asked the pilot if they knew anything about spinning and explained the PARE acronym. Pilot 3 reported that the instructor then demonstrated a spin and then allowed the pilot to handle the controls for the recovery from a second spin with the instructor following through on the controls while directing the pilot.
WebTrak data indicated the first spin occurred between 3,520 ft and 2,713 ft (807 ft altitude loss), and the second spin occurred between 3,212 ft and 2,452 ft (760 ft altitude loss). At the time, Pilot 3 did not believe the spins were prohibited because the instructor had briefed them. However, they subsequently mentioned the spins to their own HOO at Parafield, who immediately responded that they should not be doing that in a Cessna 210.
Pilot 4
Pilot 4 completed their commercial pilot licence training in 2023 and conducted 4 flights in RDH with the instructor; 2 flights on Saturday, 31 January 2026 and 2 flights on Sunday, 1 February. Pilot 4 reported that, during their first flight on 1 February, they conducted upset recovery training, which included stalls, spiral dives and spin demonstrations in which the instructor talked through the recovery actions.
After the first spin, they joined an RAAus‑registered Bristell aircraft in loose formation flying along the coast before the instructor conducted a second spin, which pilot 4 described as appearing to them to have been done within view of the Bristell pilots (Figure 6).
Figure 6: Spin activities on 1 February 2026
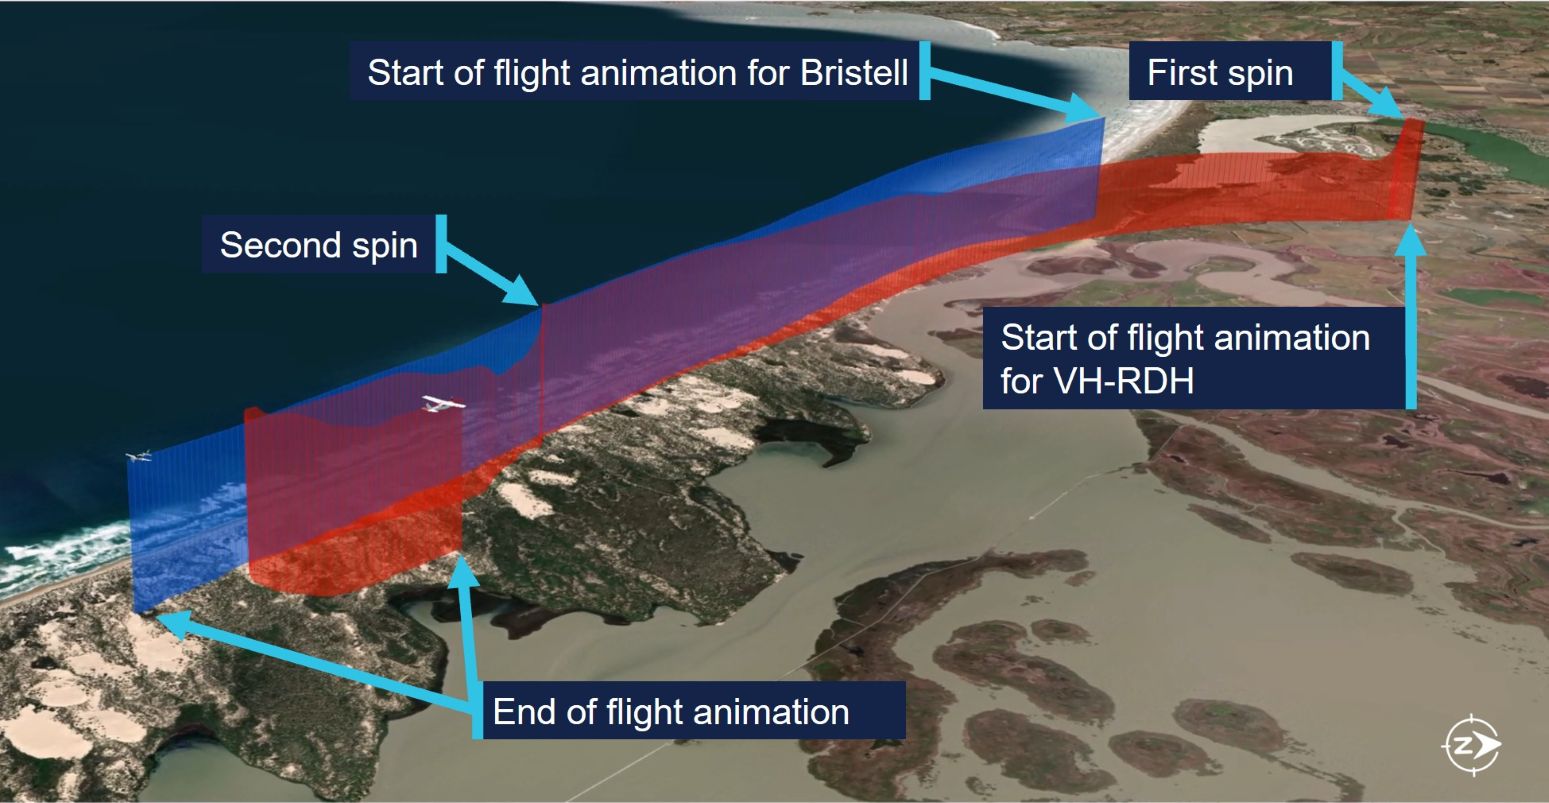
The ATSB reviewed WebTrak data of the flight and collected raw radar data, 1‑second EFB data from pilots on board both aircraft, Goolwa Airport radio recordings and interviewed both pilots on board the Bristell aircraft. The EFB data from both aircraft was entered into flight animation software and aligned by time markers to analyse the spin events. The Bristell pilot in the right seat was the HOTC from the Goolwa operator of RDH, who was also an RAAus instructor, and in the left seat was an RAAus pilot certificate holder conducting training for a navigation endorsement. Analysis of the data revealed the following sequence of events:
- RDH departed Goolwa Airport at about 1020 and conducted airwork over Hindmarsh Island, which included stalls and spiral dives.
- The Bristell departed Goolwa Airport at about 1028 and tracked south towards the coast before turning east to follow the coastline.
- RDH conducted a spin about 2.6 km north of the Bristell between 3,278 ft and 1,952 ft (1,326 ft altitude loss) and then manoeuvred to overtake the Bristell after the instructor made a radio call to the Bristell pilots that they were ‘coming down your left side’.
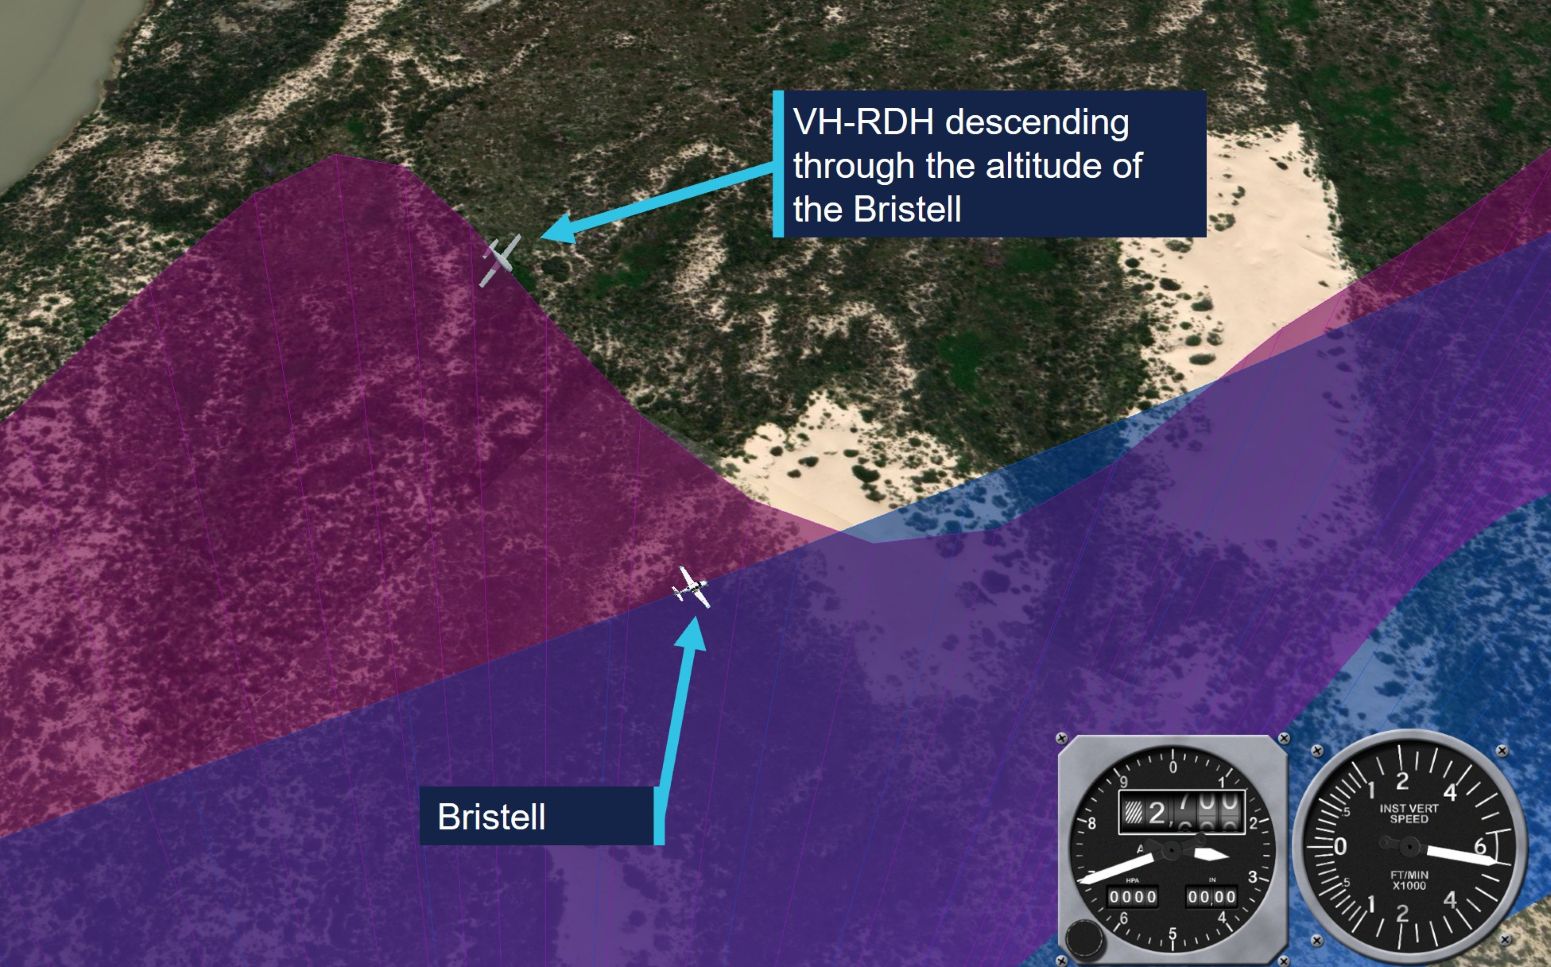
- RDH overtook the Bristell on the left side, slowed down, then pitched up (Figure 7), conducted a spin to the left between 2,953 ft and 2,008 ft (945 ft altitude loss), descending through the altitude of the Bristell slightly forward of the abeam position (Figure 8).
- The HOTC in the right seat of the Bristell saw RDH pitch up and then lost sight of it. The pilot in the left seat of the Bristell saw RDH pitch up and start to roll left before losing sight of it. Neither pilot on board the Bristell saw RDH descend.
- RDH recovered from the spin, rejoined the Bristell briefly and then conducted a wingover to the left to reverse course and returned to Goolwa Airport for circuits.
- After the spin manoeuvre, the HOTC broadcast ‘that looked a bit different’ to which the instructor on board RDH replied, ‘pitched up’. There was no reference to the spin manoeuvre.
Figure 7: VH-RDH starting to pitch up for the spin entry in front of the Bristell
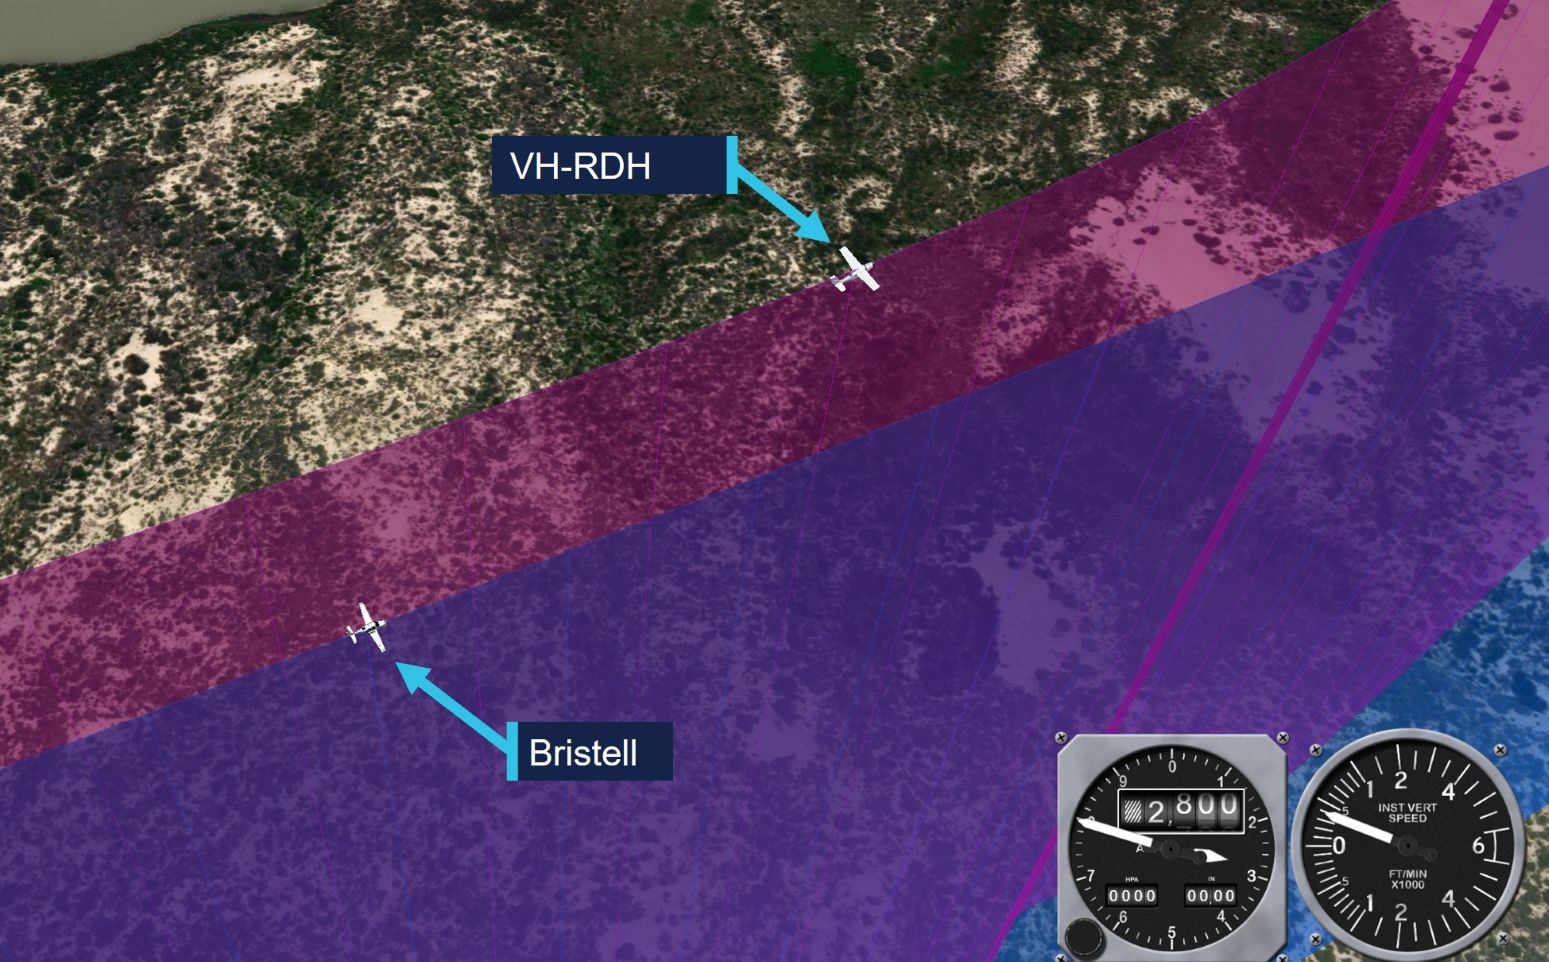
Figure 8: VH-RDH spinning abeam the Bristell
Reporting
Reporting unsafe behaviour
The majority of the spin violation incidents fell under the Goolwa operator’s safety management system and CASA unsafe behaviour system for reporting. The ATSB cannot take enforcement action for unsafe behaviour reported by witnesses or as part of the ATSB’s confidential reporting system (REPCON) and will de‑identify any individual(s) where possible when sharing information with CASA.26 Therefore, CASA may not be able to act on a report of unsafe behaviour that the ATSB has shared with them, in which case the ATSB will encourage witnesses to submit their report directly to CASA.
The aircraft operator had a reporting system in place. However, none of its pilots who experienced a spin recovery demonstration from the instructor submitted a report because they believed at the time that what the instructor did was acceptable. Likewise, none of the Cessna 210-flying experience pilots reported the spin activities to the operator because they either implicitly trusted the instructor or if they questioned the instructor, they accepted the response they received.
The instructor briefed the Goolwa operator’s HOTC on some of the activities they were conducting in RDH but reportedly omitted the upset recovery training exercises (stalls, spins and spiral dives). The HOTC reported that if they had known about the spins, they definitely would have been concerned about it. They reported that they would have first checked the POH and then spoken to the instructor. They had previously reinforced to the instructor that no spins were to be conducted in the Bristell. The ATSB interviewed an RAAus pilot certificate holder27 who had trained with the Goolwa operator, and they reported that the instructor never conducted a spin with them in the Bristell.
If CASA receives a report of unsafe behaviour, it will be referred to its response surveillance team for investigating before deciding what action is needed. While CASA is required to act in accordance with the law, it will use proportionality and discretion in regulatory decision‑making and it has a range of options available with which to respond.
The assessments by CASA for the instructor to hold the chief executive officer and HOO positions for their Part 141 approval, issued on 4 February 2026, stated that it had no recorded enforcement against the instructor. The CASA officers, interviewed by the ATSB had no knowledge of the instructor’s spin activities in RDH.
Reasons for not reporting
Several pilots, including some in management positions, had either prior personal experience or third-party knowledge of the instructor’s spin violation activities. There were some common factors provided for accepting the spin activities and not officially reporting them as unsafe behaviour. This section provides a precis of common factors from those who had personal experience of a spin violation with the instructor and perspectives from those who had third-party knowledge.
Personal experiences
- Pilot did not consider the spin was a violation at the time as the instructor was doing it. However, after the accident found out it was prohibited.
- Pilot had an aerobatics endorsement, and the aircraft was certified for spinning, so didn’t have a safety concern, but was concerned about it from a professional conduct and regulatory perspective in an RAAus-registered aircraft.
- Pilot did not question the spin at the time. However, after the accident they realised that they probably shouldn’t have been doing it.
- As a relatively inexperienced pilot with about 200 hours, they put their trust in the instructor who had a lot more experience. They found it hard to speak up and considered reporting it was easier said than done.
- Pilot immediately questioned the suggestion of a spin demonstration and the presence of a rear seat passenger but was reassured by the instructor that they had approval to do it. Trusted the instructor who had thousands of hours experience and assumed they were using the demonstration as a valuable teaching opportunity.
- Pilot had a lot of trust in the instructor and therefore assumed spinning must be allowed because the instructor had briefed it and demonstrated it.
- Only concern they had was the spinning because they checked the POH after the flight and discovered it was prohibited. However, they were comfortable with how the instructor had handled the aircraft.
Third-party knowledge
- The group at Goolwa talked about it a lot because they were a bit confused about why they were allowed to do it if it was prohibited in the POH. They felt that everyone trusted the instructor and didn’t question what the instructor did.
- Considered spinning the aircraft was inappropriate and definitely would have debriefed the instructor. While the aircraft was RAAus-registered, the seriousness of the matter was tempered by the fact that the aircraft was spin certified and the pilots were spin qualified and therefore didn’t consider it warranted external reporting. They have also been concerned about the adequacy of response from previous reports.
- The pilot who told them about the spinning didn’t seem concerned about it and they couldn’t substantiate it. As the pilot was fairly junior, they were sceptical at the time that it was actually a spin and wouldn’t report it externally without strong supporting evidence, such as a video.
- The pilots who told them about it indicated that it was allowed by the instructor. They had no experience operating a Cessna 210 and didn’t consider themselves experienced enough to challenge what an experienced instructor at another company was doing. They were also aware of previous safety concerns within the industry that they felt were not adequately addressed in a timely manner.
In addition to the above descriptions:
- The Aldinga operator HOO recalled that they might have heard a student report that the ‘world was rotating’ after a training flight with the instructor but noted that uninitiated pilots can exaggerate the description of unfamiliar manoeuvres.
- The Goolwa operator HOTC recalled that they might have heard a student report of the aircraft being ‘flipped over’ after returning from a training flight with the instructor. However, they also considered this was likely an exaggerated account from a student with no prior experience of the manoeuvre flown.
Previous occurrences
Introduction
The ATSB and NTSB databases were reviewed for Cessna 210 spin training accidents, and none were found. However, isolated cases of spin training accidents were found for the Cessna 100-series aircraft approved for intentional spinning, which included Australia, Canada and the US as detailed below.
Australia
A review of the ATSB database for spin training accidents in Cessna aircraft identified one accident for the period 2014 to 2026.
AO-2021-025: On 23 June 2021, a Cessna A150M Aerobat, with an instructor and student pilot on board entered into a left spin that started at about 6,000 ft AGL. The aircraft was not recovered from the spin and subsequently impacted terrain. The instructor and student were fatally injured, and the aircraft was destroyed. The ATSB investigation found that it was likely the instructor intended to practice spin recovery techniques on the flight and that the aircraft was most likely in the process of recovering from the spin when it impacted with trees.
It was reported that the same aircraft had not initially recovered from a spin in 1995. The 1995 spin started from 5,000 ft and the instructor directed the student to initiate the recovery at 4,300 ft, then took over control at 3,000 ft and had to coordinate full throttle with down elevator to recover control. Control was regained at 1,000 ft and the aircraft was recovered from the subsequent dive.
Canada
In 2000, the Transportation Safety Board of Canada investigated a Cessna 150M spin training accident in which no contributing factors were found. It also reviewed other unrecovered spin accidents involving Cessna 150-series aircraft in an effort to discover potential similar circumstances to the accident, but none were identified.
A00A0110: On 19 July 2000, a Cessna 150M was used by a flight instructor for a student check flight on the aircraft and local night training flight. The aircraft entered a rapid vertical descent from 3,600 ft to 2,600 ft, consistent with a spin. It then climbed to 3,800 ft, slowed down and again descended almost vertically. Eyewitnesses described it as a constant downward spiral and impacted terrain at an elevation of about 300 ft. The Board found no contributing factors and reported ‘there should not have been adverse spin characteristics or difficulty recovering.’
United States
The US National Transportation Safety Board database was interrogated for completed reports of Cessna spin accidents, which covered the period 2008 to 2024 inclusive. There were 2 that involved spin training in which the aircraft was not recovered.
CEN17FA111: On 27 February 2017, a Cessna 172S was used by a flight instructor to deliver spin training to a commercial pilot. The first spin started at 10,300 ft and descended about 1,000 ft before it recovered and climbed to 10,800 ft from which it entered a second spin. The aircraft was not recovered from the second spin and impacted a reservoir at 5,142 ft.
The 58-year old flight instructor had accumulated an estimated 6,678.5 hours and completed a check ride on the Cessna 172S. The 23-year old commercial pilot had accumulated an estimated 550 hours. The aircraft was within the utility category weight and balance limits, and no contributing factors were found. The Board concluded that ‘It is likely that the pilots did not apply prompt and/or correct flight control inputs to adequately recover from the intentional aerodynamic spin.’
WPR22FA227: On 24 June 2022, a Cessna 152 was used by a flight instructor to conduct spin training with an instructor candidate. The accident manoeuvre started at 9,100 ft and impacted terrain at an elevation of 4,590 ft. The Board found that the instructor failed to recover from a developed spin in an aircraft they only had 2.4 hours experience on and that the accident manoeuvre was commenced below the operator’s minimum altitude of 9,500 ft. There were no technical or aeromedical contributing factors, and the aircraft was within the weight and balance limits.
Safety analysis
Introduction
On 6 February 2026, a Cessna 210N, registered VH‑RDH (RDH), departed Goolwa Airport, South Australia, for a local flight with a pilot in the front left seat, flight instructor in the front right seat and passenger in the second row left seat. It initially tracked east along the coast at about 2,350 ft before reversing course and tracking west towards the Murray Mouth. As the aircraft approached Murray Mouth, the aircraft climbed to about 3,375 ft and its groundspeed slowed from 136 kt to 74 kt before entering a rapid descent. An eyewitness recorded video of the final part of the descent, which indicated the aircraft was in a left turn spin before it impacted with the water, fatally injuring the 3 occupants.
This analysis will discuss the likely purpose of the spin exercise, the likely reason why the aircraft was not recovered from the spin, the flight instructor’s health and history of spin violations, and the reporting of unsafe behaviour.
Set‑up for a spin
The ATSB received multiple reports that the flight instructor had demonstrated a spin recovery in RDH for pilots acquiring Cessna 210-flying experience through the operator and that the instructor asked some of them to follow-through on the controls. Therefore, despite the reports that it was a demonstration only and not training, the evidence indicated that on some occasions the spin activities went beyond a pure demonstration.
A student who had previously requested a spin recovery demonstration from the instructor in a Cessna 172 during their training for a recreational pilot licence, reported that 3 spin recoveries were flown. The instructor demonstrated the first spin recovery, then asked the student to follow-through on the controls for the second spin recovery, then allowed the student to manipulate the controls for the third spin recovery with the instructor following through on the controls and providing direction.
A passenger on the accident pilot's first flight in RDH reported that the instructor demonstrated a spin recovery to the pilot and then allowed the pilot to manipulate the controls under their instruction for a second spin recovery. The ATSB acknowledges that the pilot might have been following through on the controls, rather than making the inputs. However, in either case, it indicated that the instructor had progressed beyond a pure demonstration of spin recovery with the pilot in the aircraft prior to the accident flight.
The day of the accident was the pilot’s last scheduled session of flying the aircraft. In the morning, while attending a pilot maintenance training course with other Cessna 210‑flying experience pilots, the pilot reported to one witness that they planned to include airwork on their last flight and reported to another witness that they wanted to do spins.
The accident flight profile indicated the aircraft climbed above 3,000 ft and slowed towards the stall speed, which was consistent with the aircraft being set up for spin entry. This occurred in the same area the instructor had previously used for spinning the aircraft and on each occasion, the entry was flown by the instructor and the recovery conducted in the incipient phase.
The spin testing for the Cessna 210 only required the manufacturer to demonstrate recovery from an incipient spin, which allowed for recovery from a mishandled stall. It was not tested or certified for fully developed spins and intentional spinning was prohibited in the aircraft. Therefore, its behaviour and recovery in a fully developed spin was unknown and it could potentially be resistant to recovery or susceptible to an extended recovery.
The ATSB considered the possibility that the instructor may have attempted to demonstrate a fully developed spin. However, the instructor had been teaching spinning since 2009, had demonstrated knowledge of aircraft spin certification standards for other aircraft and every report of a spin violation in RDH was of an incipient spin, which indicated the instructor likely understood the certification standards. Therefore, it was considered unlikely that the instructor intentionally set up the aircraft to perform a fully developed spin.
Given the witness accounts and video of the accident descent, the instructor’s history with the pilot and the accident flight profile, the ATSB considered it likely that the instructor conducted a spin entry to allow the pilot to attempt a spin recovery during the incipient spin phase.
Contributing factor It was likely that the instructor conducted a spin entry for the purpose of the pilot practicing the spin recovery actions, which was conducted in an aircraft that was not approved for intentional spins and from which a fully developed spin could be difficult to recover. |
Inadequate intervention
As discussed, the ATSB considered it unlikely that the accident was the result of the aircraft intentionally being established in a fully developed spin. Rather, the available evidence indicated it was likely that the flight instructor initiated a spin for the purpose of the pilot practicing the recovery actions in the incipient phase. The pilot had previously seen a demonstration spin recovery and had reportedly handled the controls on a second spin recovery.
Video analysis revealed there was a significant reduction in the rate of spin just prior to the collision with water, which indicated that the aircraft was responding to spin recovery inputs. While the flight controls were subject to maintenance in September 2025, the tasks were correctly certified with independent inspections, and the instructor had conducted several incipient spins in the aircraft since the maintenance and prior to the accident flight. None of the interviewees reported a flight control problem with the aircraft and the pilot maintenance training activities on the day of the accident did not disturb the flight controls. Therefore, a contributing technical fault was considered unlikely.
The Cessna 210N was not certified to the standard for intentional spinning, which required fully developed spin testing. Therefore, there was no assurance of an adequate margin of safety if an incipient spin was mishandled and it entered a fully developed spin. There have been isolated accidents around the world involving spin training in Cessna 100-series spin approved aircraft with no contributing factors identified to prevent the recovery. However, the manufacturer’s guide for the spin characteristics of its aircraft approved for intentional spinning identified some of the incorrect recovery actions that could contribute to an accelerated rotation and/or lengthened recovery. They included incorrect sequence of actions, incorrect control positions, slow rate of application and premature relaxation of inputs.
The instructor did not provide any ground instruction or pre-flight briefing on spins to the Cessna 210-flying experience pilots. The spin exercises were reported to the ATSB as only being raised by the instructor after becoming airborne. Consequently, they only received a short inflight brief that focused on the correct recovery technique based on the PARE acronym. Therefore, it was unlikely that the accident pilot understood how a spin could be mishandled to produce an accelerated rotation and/or lengthened recovery or that it was a prohibited intentional manoeuvre in the Cessna 210N.
In consideration of these factors, the ATSB considered it likely that the pilot mishandled the recovery from an incipient spin that they had not been adequately trained to conduct and in an aircraft that was not approved for intentional spinning, and that the instructor did not effectively intervene in sufficient time to prevent the aircraft from entering a fully developed spin and recover within the height available.
Contributing factor It was likely that the pilot mishandled the recovery from an intentional incipient spin and the instructor did not intervene in sufficient time to prevent the aircraft entering a fully developed spin and recover within the height available. |
Flight instructor’s health
The flight instructor received an intermediate risk score for cardiovascular disease at their last aviation medical exam (corrected from low risk). The pathologist subsequently found evidence of severe coronary artery narrowing, which meant that a medical event could not be excluded or confirmed pathologically. The Civil Aviation Safety Authority (CASA) agreed with the pathologist’s conclusion and noted that the autopsy findings indicated that the instructor’s risk of cardiovascular disease was higher than predicted by their last aviation medical exam.
Consequently, the ATSB considered the possibility of a medical event that affected the instructor’s ability to intervene and recover the aircraft during the spin. Noting the aircraft was recovering from the spin prior to the collision, and only the instructor was trained to recover from a spin, it was considered most likely that the instructor was handling the controls at this stage. Furthermore, the nose-down elevator trim condition of the aircraft could also be an indicator of the instructor’s efforts to unstall the wings and regain control of the aircraft.
Therefore, while the severity of the instructor’s coronary artery disease indicated an increased risk of a loss of control event from incapacitation, it could not be concluded that a medical event was a likely contributing factor.
Other factor that increased risk The flight instructor's post-mortem examination indicated that they were at a higher risk of a cardiovascular medical event than predicted by their aviation medical exam, but it could not be determined if it contributed to the accident. |
History of spin violations
The flight instructor demonstrated spin recoveries in RDH for several pilots, including with a passenger on board, over a period of about 2 months prior to the accident flight. This included 2 spin demonstrations the weekend prior to the accident, with the second spin conducted between 3,000 ft and 2,000 ft in close proximity to another aircraft without any warning to the crew of that aircraft. This was below the manufacturer’s recommendation for their spin-approved aircraft to enter spins at sufficient altitude to recover by 4,000 ft above terrain.
The instructor’s aerobatics endorsement was lowered from 3,000 ft to 1,500 ft in November 2025, the month prior to the first report of them conducting a spin recovery demonstration in RDH. The regulatory height limit for spinning was in accordance with the respective pilot’s aerobatic endorsement limit and any applicable flight manual limits. The aircraft was not approved for intentional spinning but had been successfully tested for recovery from an incipient spin, and the spins the instructor conducted in RDH were recovered in about 800–1,300 ft,28 which was consistent with incipient spins.
The reported spins in December 2025 started at about 4,500 ft, in January 2026 at about 3,500 ft, and in February 2026, a week prior to the accident, at about 3,000 ft. The lowest recorded recovery altitude found in the data was 1,952 ft on the weekend prior to the accident. Therefore, the instructor consistently recovered above their aerobatics height limit of 1,500 ft and always in the incipient phase, but by February 2026, they had significantly lowered their spin entry heights in RDH from December 2025.
The lowering of the entry height was likely an indicator of an increase in the instructor's confidence in their ability to recover the aircraft during the incipient phase and above their aerobatic height limit. The accident spin entry height was about 1,000 ft lower than the entry heights the instructor used 2 months earlier when they started the spin activities in RDH. Given that the video evidence indicated the aircraft was recovering from the spin just prior to the collision, it was likely that it could have been recovered if the instructor had not lowered the entry height they were using.
Contributing factor The instructor had a history of spin activity violations from which they successfully recovered during the incipient phase, which likely provided them with the confidence to progressively lower the entry height they were using. |
Reporting unsafe behaviour
The aircraft operator had a safety management system with a safety reporting system in place. However, none of its pilots who experienced a spin with the flight instructor, in violation of the respective pilot operating handbook, submitted a report. Likewise, none of the Cessna 210-flying experience pilots reported the spin activities to the operator. The instructor briefed the operator’s head of training and checking (HOTC) on some of the activities they were conducting in RDH but reportedly omitted the upset recovery training activities, which the HOTC remained unaware of.
The HOTC reported that if they had known about the instructor conducting spins in RDH, they would definitely have been concerned about it. They reported that they would have checked the pilot operating handbook and then spoken to the instructor about it, and that they had previously advised the instructor not to spin aircraft that were not approved for intentional spinning, specifically the Bristell.
The CASA website for reporting unsafe behaviour stated that a report will be added to the individual's or organisation's file. However, nobody submitted a report to CASA and the CASA file for the instructor did not contain any reports of unsafe behaviour. In addition, the CASA officers interviewed by the ATSB had no knowledge of any spin violation activities by the instructor. CASA is obliged to act on reports of unsafe behaviour and have an established process in such circumstances to ensure a proportionate outcome is achieved based on the evidence available.
Interviewees provided a range of reasons for not officially reporting their knowledge of the activities, which included the following issues:
- trust – assumed it must have been allowed since they were doing it
- experience gradient – accepted the instructor’s assurance when questioned
- concern about potentially causing trouble
- uncertainty/disbelief that reports of the activities were true
- belief that it wasn't their responsibility to get involved
- lack of confidence in reporting outcomes.
The issues of trust, experience gradient, and concern about causing trouble, were themes among those relatively young and new to aviation in comparison to the instructor. These issues appeared despite some of the pilots learning that intentional spinning of the aircraft was prohibited and suggested that they did not believe that they had the power to deal with the situation (power to act).
The issues of disbelief, lack of responsibility, and lack of confidence in reporting, were themes among those who were more experienced and remote from the activities. This suggested they did not believe that they had the job or duty to deal with the situation (duty to act). These 2 separate ideas of power to act and duty to act indicated that the promotion of reporting systems could benefit from messages tailored for different audience members to address their specific concerns towards reporting flight discipline events.
If a report had been submitted to the operator or CASA, it could have been verified with recorded data, either from the reporter or from publicly available data. Therefore, the ATSB considered it likely that either the operator or CASA could have initiated action to intervene and stop the instructor’s spin activities in RDH.
Contributing factor The flight instructor's spin violations were not reported to the operator or the Civil Aviation Safety Authority, and therefore no action was taken to stop these activities. |
Findings
ATSB investigation report findings focus on safety factors (that is, events and conditions that increase risk). Safety factors include ‘contributing factors’ and ‘other factors that increased risk’ (that is, factors that did not meet the definition of a contributing factor for this occurrence but were still considered important to include in the report for the purpose of increasing awareness and enhancing safety). In addition ‘other findings’ may be included to provide important information about topics other than safety factors. These findings should not be read as apportioning blame or liability to any particular organisation or individual. |
From the evidence available, the following findings are made with respect to the loss of control and collision with water involving Cessna 210N, VH‑RDH, 14 km south-east of Goolwa Airport, South Australia, on 6 February 2026.
Contributing factors
- It was likely that the instructor conducted a spin entry for the purpose of the pilot practicing the spin recovery actions, which was conducted in an aircraft that was not approved for intentional spins and from which a fully developed spin could be difficult to recover.
- It was likely that the pilot mishandled the recovery from an intentional incipient spin and the instructor did not intervene in sufficient time to prevent the aircraft entering a fully developed spin and recover within the height available.
- The instructor had a history of spin activity violations from which they successfully recovered during the incipient phase, which likely provided them with the confidence to progressively lower the entry height they were using.
- The flight instructor's spin violations were not reported to the operator or the Civil Aviation Safety Authority, and therefore no action was taken to stop these activities.
Other factors that increased risk
- The flight instructor's post-mortem examination indicated that they were at a higher risk of a cardiovascular medical event than predicted by their aviation medical exam, but it could not be determined if it contributed to the accident.
Sources and submissions
Sources of information
The sources of information during the investigation included:
- accident witnesses
- Airservices Australia
- Bureau of Meteorology
- Civil Aviation Safety Authority
- electronic flight bag app developers
- maintenance organisation for Goolwa operator
- next of kin
- operators from Aldinga, Goolwa and Parafield
- pilots who flew with the instructor
- South Australia Police
- Textron Aviation Inc.
- Transportation Safety Board of Canada
- United Kingdom Civil Aviation Authority
- United States Federal Aviation Administration
- United States National Transportation Safety Board
- video footage of the accident flight and other photographs and videos taken.
References
Cessna (1981). Spin characteristics of Cessna Models 150, A150, 152, A152, 172, R172 & 177 (D5014-2-13—CES—1700—12/81), copy provided by Textron Aviation Inc.
Civil Aviation Safety Authority (2007). Flight instructor manual (aeroplane), accessed 28 May 2026.
Civil Aviation Safety Authority (2020). Spin avoidance and stall recovery training (Advisory circular 61-16 v1.0), accessed 11 March 2026.
Federal Aviation Administration (1972). Engineering flight test guide for small airplanes (8110.7), copy provided by Textron Aviation Inc.
Submissions
Under section 26 of the Transport Safety Investigation Act 2003, the ATSB may provide a draft report, on a confidential basis, to any person whom the ATSB considers appropriate. That section allows a person receiving a draft report to make submissions to the ATSB about the draft report.
A draft of this report was provided to the following directly involved parties:
- aircraft operator
- Civil Aviation Safety Authority
- United States National Transportation Safety Board
- Textron Aviation Inc.
Submissions were received from:
- operator from Aldinga
- Civil Aviation Safety Authority.
The submissions were reviewed and, where considered appropriate, the text of the report was amended accordingly.
Purpose of safety investigationsThe objective of an ATSB safety investigation is to improve transport safety through:
In accordance with the TSI Act, the ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action, and cannot apportion blame, assist in determining liability, or, as a general rule, assist in court proceedings. About ATSB reportsATSB safety investigation reports are developed in accordance with ATSB procedures and guidelines, and with regard to applicable international standards and instruments. Reports must include factual material of sufficient weight to support the investigation’s analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. An explanation of terminology used in ATSB investigation reports is available here. Publishing informationReleased in accordance with section 25 of the Transport Safety Investigation Act 2003 Published by: Australian Transport Safety Bureau © Commonwealth of Australia 2026 Ownership of intellectual property rights in this publication Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia. Creative Commons licence 
With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence. The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly. |
- ^ Uncorrected altitude data was based on the standard atmosphere altimeter pressure setting of 1013 hPa, rounded to the nearest hundred feet.
- ^ All speeds in the report are ATC-recorded groundspeeds.
- ^ ATC calculated barometric altitude was based on the Adelaide altimeter pressure setting of 1015 hPa.
- ^ CTAF: common traffic advisory frequency is the radio frequency used by pilots when operating in the vicinity of non‑towered airports.
- ^ The Type Certificate Holder was transferred to Textron Aviation Inc. on 29 July 2015.
- ^ The US Code of Federal Regulations (CFR) 23.1559 required the Operating limitations placard to be ‘in clear view of the pilot’ and was included in the certification basis for the Cessna 210N. However, CFR 23.1559 did not define what ‘in clear view of the pilot’ meant. CFR 23.1567 stated that the flight manoeuvre placard must be ‘in front of and in clear view of the pilot’, but CFR 23.1567 was not included in the certification basis for the Cessna 210N.
- ^ The US Federal Aviation Administration Engineering Flight Test Guide for Small Airplanes (1972) defined the recovery as the dive and pullout after rotation has ceased (8110.7).
- ^ A coordinated positive g pitching and rolling manoeuvre.
- ^ The HOTC was also the HOO for the Goolwa operator. However, HOTC is used in the report to distinguish this person from the Aldinga operator HOO.
- ^ The flight instructor remained a casual employee through to the accident.
- ^ All the pilots on the Cessna 210-flying experience package interviewed by the ATSB reported that they were directed by the instructor to log their first 2 flights as pilot-in-command-under-supervision and the remainder as PIC. However, the instructor logged ‘Command’ time against all of their flights, and the interviews indicated that the pilots received instruction on their first 2 flights and operated in-command-under-supervision for the remainder of their flights.
- ^ Circuit training is one of the first stages of practical pilot training, focused on take-offs and landings. It involves the pilot making approaches to the runway, touching down and then applying power to take-off again.
- ^ Several of the Cessna 210-flying experience pilots stated that they expected the first day of training to include a review of the POH with the instructor, but this did not occur. Civil Aviation Safety Regulation 61.385 specifies the general competency requirements to exercise the privileges of a licence in an aircraft, which includes the material contained within the POH. However, compliance with 61.385 is a licence holder responsibility.
- ^ The witnesses were Cessna 210-flying experience pilots attending the pilot maintenance training.
- ^ The maximum take-off weight for the Cessna 210N was 3,800 lb (1,724 kg).
- ^ ‘Not detected’ signified the drug(s) were not detected above the laboratory’s limit of reporting.
- ^ This was later corrected to be 6% and an intermediate risk.
- ^ Low-density lipoprotein (LDL) is a cholesterol that can stick to the walls of arteries and cause a fatty build‑up called plaque. Too much plaque leads to blockages that prevent blood from flowing properly to the heart (Manage high blood cholesterol levels | Heart Foundation). Rosuvastatin and Ezetimibe are prescription medicines that help lower LDL in the blood.
- ^ The higher corrected CVD score of 6% and intermediate risk would not have prevented the instructor being re‑issued with a Class 1 medical certificate.
- ^ CASA obtained similar results from the CVD calculators used by the United Kingdom and US regulators when they input the instructor’s data.
- ^ Decision amending Acceptable Means of Compliance (AMC) and Guidance Material (GM) for UK Regulation (EU) 2019/947.
- ^ RAAus did not have a syllabus for spin training and therefore RAAus-registered aircraft could not be used for this purpose regardless of their certification.
- ^ The Cessna 172R is certified in the normal and utility categories. In the utility category the maximum gross weight and aft centre-of-gravity limits are restricted to less than those allowed in the normal category.
- ^ At the time, both row 2 seats had been temporarily removed to carry cargo.
- ^ Pilot 1 reported overhearing this exchange between pilot 2 and the instructor on the intercom.
- ^ The exception to this is if there is an imminent risk to safety.
- ^ This was the RAAus pilot certificate holder involved in the incident on 1 February 2026 who reported that the accident flight instructor had delivered about half their flight training.
- ^ Where recorded data was available, recovered and analysed.
Preliminary report
Report release date: 04/03/2026
| This preliminary report details factual information established in the investigation’s early evidence collection phase and has been prepared to provide timely information to the industry and public. Preliminary reports contain no analysis or findings, which will be detailed in the investigation’s final report. The information contained in this preliminary report is released in accordance with section 25 of the Transport Safety Investigation Act 2003. |
The occurrence
On 6 February 2026, at about 1608 local time, a Cessna 210N, registered VH-RDH, departed from Goolwa Airport, South Australia, with 3 persons on board for a private local area flight. The persons on board comprised a flight instructor in the front right seat, a commercial pilot licence holder in the front left seat and a passenger, who held a recreational pilot licence, in the second row left seat. The purpose of the flight was for the commercial pilot licence holder to accumulate Cessna 210 flying experience. This was conducted under the supervision of the aircraft operator’s head of training and checking, who was the onboard flight instructor.
Air Traffic Control (ATC) radar detected the aircraft at 1609:45 and the ATC system started generating a track for the aircraft at 1609:50 at an uncorrected altitude[1] of 1,100 ft and groundspeed of 93 kt. Calculated barometric altitude[2] started at 1609:58 and recorded the aircraft at 1,275 ft and a groundspeed of 93 kt.[3] Goolwa Airport CTAF[4] recordings captured a runway 19 upwind departure call from the instructor, that they were climbing through 1,000 ft to 1,500 ft and tracking coastal to the east. The departure call was followed by an amendment that the aircraft was climbing to 2,500 ft for smoother air.
ATC radar tracked the aircraft as it followed the coast to the east at about 2,350 ft for about 5 minutes at about 130 kt. The aircraft then commenced a right turn through south to track west along the coast back towards the mouth of the Murray River (Murray Mouth) at about 136 kt. As the aircraft approached Murray Mouth, the altitude increased and reached 3,375 ft at 1620:52. As the aircraft climbed above 3,000 ft the tracking data shifted slightly south (at 1620:17) and the speed reduced to 74 kt while maintaining a westerly track.
At 1620:57 the aircraft was recorded at an uncorrected altitude of 2,700 ft, still on a westerly track, and the speed had reduced to 66 kt. The ATC system then ceased tracking the aircraft, but it was captured a final time on radar at 1621:05, at an uncorrected altitude of 1,200 ft. Figure 1 depicts the accident flight with 4 data points annotated.
Figure 1: Air traffic control generated track with data points annotated

Airservices Australia generated tracking data for the accident flight with ATSB numbered data points – at data point 2 the aircraft has climbed above 3,000 ft and the track has shifted to the south. Source: Airservices Australia, annotated by the ATSB
A witness located on the west side of Murray Mouth observed the aircraft in a steep descent and used their phone to record the final seconds of the descent. The footage indicated the aircraft was in a left turn spin just prior to colliding with the water in a steep nose down and left-wing low attitude, intact with the landing gear retracted. Several witnesses reported to the ATSB that the engine sounded like it was running until the collision. The 3 occupants were fatally injured and the aircraft was destroyed.
Wreckage inspection
The wreckage was retrieved from the water by South Australia Police prior to the ATSB’s arrival at the site on the afternoon of 7 February 2026. The wreckage was heavily fragmented and missing the engine, propeller, wings, vertical fin and rudder. The main gear was found down and locked and the nose gear retracted. Several seat belts had been cut by emergency services personnel to remove the occupants.
The left front seat was attached to the seat rails and fitted with an inertial reel strap to prevent inadvertent movement in flight. The strap was cut to remove the seat from the aircraft. The front right seat had separated from the seat rails, but the seat lock pins were in the down (locked) position and appeared undamaged. The second row left seat had separated from the floor of the aircraft but was contained within the wreckage. The second row right seat was not fitted. The rear seats (third row) were attached to the airframe.
The elevator control cables were identified, and the elevator trim surface was present and attached to the elevator. The elevator was free to move in the correct sense. Measurements of the elevator trim position were made, and an elevator control cable turnbuckle was removed and, in addition to the aircraft global positioning system unit, retained for further examination.
Further investigation
To date, the ATSB has:
- inspected the wreckage and the departure airport’s fuel supply
- recovered and retained equipment for further examination
- collected records from the aircraft operator and Civil Aviation Safety Authority
- collected air traffic control and airport data
- collected electronic flight bag data
- interviewed witnesses and other Cessna 210 pilots.
The investigation is continuing and will include:
- further interviews
- a review of aircraft operator and Civil Aviation Safety Authority records
- analysis of witness videos, photographs, airport data and interviews
- analysis of data from air traffic control, electronic flight bags and from equipment recovered from the aircraft.
A final report will be released at the conclusion of the investigation. Should a critical safety issue be identified during the course of the investigation, the ATSB will immediately notify relevant parties so appropriate and timely safety action can be taken.
Acknowledgements
The ATSB acknowledges the assistance provided by South Australia Police and State Emergency Service personnel.
Purpose of safety investigationsThe objective of a safety investigation is to enhance transport safety. This is done through:
It is not a function of the ATSB to apportion blame or provide a means for determining liability. At the same time, an investigation report must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. The ATSB does not investigate for the purpose of taking administrative, regulatory or criminal action. About ATSB reportsATSB investigation reports are organised with regard to international standards or instruments, as applicable, and with ATSB procedures and guidelines. Reports must include factual material of sufficient weight to support the analysis and findings. At all times the ATSB endeavours to balance the use of material that could imply adverse comment with the need to properly explain what happened, and why, in a fair and unbiased manner. An explanation of terminology used in ATSB investigation reports is available here. This includes terms such as occurrence, contributing factor, other factor that increased risk, and safety issue. Publishing informationReleased in accordance with section 25 of the Transport Safety Investigation Act 2003 Published by: Australian Transport Safety Bureau © Commonwealth of Australia 2026 
Ownership of intellectual property rights in this publication Unless otherwise noted, copyright (and any other intellectual property rights, if any) in this report publication is owned by the Commonwealth of Australia. Creative Commons licence With the exception of the Commonwealth Coat of Arms, ATSB logo, and photos and graphics in which a third party holds copyright, this report is licensed under a Creative Commons Attribution 4.0 International licence. The CC BY 4.0 licence enables you to distribute, remix, adapt, and build upon our material in any medium or format, so long as attribution is given to the Australian Transport Safety Bureau. Copyright in material obtained from other agencies, private individuals or organisations, belongs to those agencies, individuals or organisations. Where you wish to use their material, you will need to contact them directly. |
[1] Uncorrected altitude data was based on the standard atmosphere altimeter pressure setting of 1013 hPa, rounded to the nearest hundred feet.
[2] The calculated barometric altitude was based on the Adelaide altimeter pressure setting of 1015 hPa.
[3] All speeds in the report are ATC-recorded groundspeeds.
[4] CTAF: common traffic advisory frequency is the radio frequency used by pilots when operating in the vicinity of non‑towered airports.
Occurrence summary
| Investigation number | AO-2026-010 |
|---|---|
| Occurrence date | 06/02/2026 |
| Occurrence time and timezone | 1621 Central Australian Daylight saving Time |
| Location | 14 km south-east of Goolwa Airport |
| State | South Australia |
| Report release date | 28/10/2026 |
| Report status | Final |
| Investigation type | Occurrence Investigation |
| Investigation phase | Final report: Dissemination |
| Investigation status | Completed |
| Mode of transport | Aviation |
| Aviation occurrence category | Collision with terrain |
| Occurrence class | Accident |
| Highest injury level | Fatal |
Aircraft details
| Manufacturer | Cessna Aircraft Company |
|---|---|
| Model | 210N |
| Registration | VH-RDH |
| Serial number | 21064374 |
| Aircraft operator | Goolwa Air Pty Ltd |
| Sector | Piston |
| Operation type | Part 91 General operating and flight rules |
| Activity | General aviation / Recreational-Other general aviation flying-Other flights |
| Departure point | Goolwa Aircraft Landing Area, South Australia |
| Destination | Goolwa Aircraft Landing Area, South Australia |
| Injuries | Crew - 2 (fatal), Passengers - 1 (fatal) |
| Damage | Destroyed |